


Product Monograph - Alertec
RECENT MAJOR LABEL CHANGES
| N/A |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ...................................................................................... 2
TABLE OF CONTENTS ........................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ........................................................................................................... 4
1.2 Geriatrics ........................................................................................................... 5
2 CONTRAINDICATIONS ................................................................................................ 5
4 DOSAGE AND ADMINISTRATION .............................................................................. 5
4.1 Dosing Considerations ....................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................... 6
4.5 Missed Dose ...................................................................................................... 7
5 OVERDOSAGE ............................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................... 7
7 WARNINGS AND PRECAUTIONS ............................................................................... 8
7.1 Special Populations ......................................................................................... 13
7.1.1 Pregnant Women ......................................................................................... 13
7.1.2 Breast-feeding .............................................................................................. 14
7.1.3 Pediatrics ..................................................................................................... 14
7.1.4 Geriatrics ..................................................................................................... 15
8 ADVERSE REACTIONS ............................................................................................. 15
8.1 Adverse Reaction Overview ............................................................................. 15
8.2 Clinical Trial Adverse Reactions ....................................................................... 15
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ............................................... 18
8.3 Less Common Clinical Trial Adverse Reactions ............................................... 18
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ......................................................................................................... 19
8.5 Post-Market Adverse Reactions ....................................................................... 20
9 DRUG INTERACTIONS .............................................................................................. 20
9.2 Drug Interactions Overview .............................................................................. 20
9.3 Drug-Behavioural Interactions .......................................................................... 21
9.4 Drug-Drug Interactions ..................................................................................... 21
9.5 Drug-Food Interactions .................................................................................... 25
9.6 Drug-Herb Interactions ..................................................................................... 25
9.7 Drug-Laboratory Test Interactions .................................................................... 25
10 CLINICAL PHARMACOLOGY .................................................................................... 25
10.1 Mechanism of Action ........................................................................................ 25
10.2 Pharmacodynamics ......................................................................................... 26
10.3 Pharmacokinetics ............................................................................................. 27
11 STORAGE, STABILITY AND DISPOSAL ................................................................... 28
12 SPECIAL HANDLING INSTRUCTIONS ...................................................................... 28
PART II: SCIENTIFIC INFORMATION ................................................................................... 29
13 PHARMACEUTICAL INFORMATION ......................................................................... 29
14 CLINICAL TRIALS ...................................................................................................... 29
14.1 Clinical Trials by Indication ............................................................................... 29
Narcolepsy .................................................................................................................. 29
Obstructive Sleep Apnea (OSA) .................................................................................. 31
Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder) (SWD) ....... 32
14.2 Comparative Bioavailability Study .................................................................... 33
15 MICROBIOLOGY ........................................................................................................ 34
16 NON-CLINICAL TOXICOLOGY .................................................................................. 34
PATIENT MEDICATION INFORMATION ............................................................................... 39
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
ALERTEC (modafinil) is indicated for:
The symptomatic treatment of excessive sleepiness in adult patients with narcolepsy.
In narcolepsy, ALERTEC has no significant effect on cataplexy.
The symptomatic treatment of excessive sleepiness in adult patients with obstructive sleep apnea (OSA).
In OSA, ALERTEC is indicated as an adjunct to successful standard treatment(s) for the underlying obstruction, when excessive sleepiness persists. If continuous positive airway pressure (CPAP) is the treatment of choice for a patient with OSA, a maximal effort to treat with CPAP for an adequate period of time should be made prior to initiating ALERTEC. If ALERTEC is used adjunctively with CPAP, the encouragement of and periodic assessment of CPAP compliance is necessary.
The symptomatic treatment of excessive sleepiness in adult patients with circadian rhythm sleep disorder, shift work type (shift work disorder) (SWD).
In SWD, ALERTEC (modafinil) is indicated for the symptomatic treatment of excessive sleepiness (as confirmed by multiple sleep latency test) associated with loss of a normal sleep-wake pattern (as confirmed by polysomnography).
Daytime sleep (as measured by polysomnography) in SWD is not affected by the use of ALERTEC.
The effect of ALERTEC on night-shift work performance, sleep deficit in SWD, or performance following a night-shift have not been adequately evaluated in controlled studies.
The effectiveness of modafinil in long-term use (greater than 9 weeks in the narcolepsy clinical trials and 12 weeks in the OSA and SWD clinical trials) has not been systematically evaluated in placebo-controlled trials. The physician who elects to prescribe ALERTEC for an extended time in patients with narcolepsy, OSA or SWD should periodically re-evaluate long-term usefulness for the individual patient.
ALERTEC should not be used for the treatment of normal fatigue states. The safety and efficacy of ALERTEC has not been studied in this patient population (see 7 WARNINGS AND PRECAUTIONS, General).
There is no evidence that normal levels of alertness can be heightened by ALERTEC.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and effectiveness in pediatric patients have not been established (see 7.1.3 Pediatrics and 8.2.1 Clinical Trial Adverse Reactions – Pediatric). Therefore, ALERTEC is not approved for use in pediatric patients for any indication including Attention Deficit Hyperactivity Disorder (ADHD).
Serious cutaneous adverse reactions have been reported with modafinil use in pediatric patients (see 7 WARNINGS AND PRECAUTIONS, Skin).
1.2 Geriatrics
Geriatrics (>65 years old): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
ALERTEC is contraindicated:
- In patients who are hypersensitive to modafinil, armodafinil (the R-enantiomer of modafinil; not marketed in Canada) or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- In patients in agitated states and in patients with severe anxiety.
- In women who are pregnant or may become pregnant. Women should be advised regarding the use of effective contraception during treatment as modafinil may reduce effectiveness of steroidal contraceptives (see 4.1 Dosing Considerations, 7.1.1 Pregnant Women).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- A cardiac evaluation, including an electrocardiogram (ECG), should be obtained for all patients before treatment with ALERTEC is initiated. This is particularly recommended for patients with coronary artery disease, a recent history or myocardial infarction, or unstable angina. Patients with abnormal findings should receive further evaluation before ALERTEC treatment is considered. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular.
- Based on post-marketing reports, modafinil may cause fetal harm and is contraindicated in women who are pregnant or may become pregnant (see 2 CONTRAINDICATIONS and 7.1.1 Pregnant Women). Women of reproductive potential should have a negative pregnancy test within a week prior to starting treatment with modafinil.
- The effectiveness of steroidal contraceptives may be reduced due to induction of CYP3A4/5 by modafinil (see 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions). Alternative or concomitant methods of contraception other than steroidal are recommended for patients treated with ALERTEC, and for two months after discontinuation of ALERTEC.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
Narcolepsy: The adult daily dosage of ALERTEC (modafinil) for patients with narcolepsy is between 200 to 400mg, divided between morning and noon doses. The initial daily dose should be 200mg in divided doses, increasing in increments of 100mg as needed and tolerated.
The total daily dose can be divided according to the needs and response of the patient. The timing should be aimed to coincide with the periods of greatest excessive daytime sleepiness. The second dose should generally be taken no later than the early afternoon to minimize the risk of insomnia.
Although the occasional patient may need and tolerate daily doses of 500mg, limited data from trials in healthy volunteers suggest that the number and type of side effects increase significantly after single doses of 300mg and after total daily doses of more than 400mg, compared to 100 and 200mg doses b.i.d. Single doses of 300mg or more, or total daily doses of more than 400mg are therefore not recommended.
Obstructive Sleep Apnea: In OSA, ALERTEC is indicated as an adjunct to successful standard treatment(s) for the underlying obstruction (see 1 INDICATIONS). For patients with OSA, the adult daily dosage of ALERTEC is 200mg taken as a single dose in the morning.
Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder): For patients with SWD, the adult daily dosage of ALERTEC is 200mg taken approximately 1 hour prior to the start of their work shift.
Dosage Adjustment
Pediatric (<18 years of age)
The safety and efficacy of modafinil in children under the age of 18 years has not been established. Therefore, modafinil is not indicated for use in pediatric patients (see 1.1 Pediatrics).
Geriatric
In geriatric patients, elimination of ALERTEC and its metabolites may be reduced as a consequence of aging. Therefore, consideration should be given to the use of lower doses in this population (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
Severe Hepatic Impairment
In patients with severe hepatic impairment, the dose of ALERTEC should be reduced to one-half of the usual recommended dose (see 10.3 Pharmacokinetics).
Concomitant use with CYP3A4 substrates
Dosage adjustment should be considered for concomitant medications that are substrates for CYP3A4, such as triazolam and cyclosporine (see 7 WARNINGS AND PRECAUTIONS, General, 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions).
Concomitant use with CYP2C19 substrates
Because modafinil and its metabolite, modafinil sulfone, are reversible inhibitors of the drug-metabolizing enzyme CYP2C19, co-administration of modafinil with drugs which are largely eliminated via that pathway may increase the circulating levels of those compounds, which may have prolonged elimination upon co-administration with ALERTEC and may require dosage reduction and monitoring for toxicity (see 9.2 Drug Interactions Overview).
4.5 Missed Dose
If a dose is missed, it can be taken when remembered, unless it is close to the time for the next dose. Taking the medication in the evening or the late afternoon may prevent from falling asleep at usual bedtime, and should, therefore, be avoided.
5 OVERDOSAGE
Symptoms most often accompanying ALERTEC overdose, alone or in combination with other drugs have included insomnia; central nervous system symptoms such as restlessness, disorientation, confusion, agitation, anxiety, excitation and hallucination; digestive changes such as nausea and diarrhea; and cardiovascular changes such as tachycardia, bradycardia, hypertension, and chest pain.
Intentional overdose by patients have been reported, where death has occurred with modafinil, either alone (dose 72 grams) or in combination with other drugs (dose from 200mg up to 6000mg).
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1– Dosage Forms, Strengths, Composition and Packaging
Each white to off-white capsule shaped tablet of ALERTEC, debossed with "100" on one side, contains modafinil 100mg.
- Available in blister strips of 10 tablets, in packages of three strips.
- Available in bottles of 100 tablets
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablet 100 mg | Lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, pregelatinized starch, sodium croscarmellose |
7 WARNINGS AND PRECAUTIONS
General
Persistent Sleepiness: Patients with abnormal levels of sleepiness who take ALERTEC should be advised that their level of wakefulness may not return to normal. Patients with excessive sleepiness, including those taking ALERTEC, should be frequently reassessed for their degree of sleepiness and, if appropriate, advised to avoid driving or any other potentially dangerous activity.
Normal Fatigue States: ALERTEC should not be used for the treatment of normal fatigue states. One preliminary study in sleep-deprived subjects, employing a between-subject design (n=42) and a single dose (300mg), suggests that ALERTEC causes an increased self-estimate of performance which is not commensurate with actual changes in performance (i.e., overconfidence). A subsequent study in sleep-deprived subjects, employing a within-subject design (n=6), using 100mg administered three times over a period of 24 hours failed to demonstrate an adverse effect on the ability to judge one’s own cognitive capabilities.
Use in Combination with Other CNS Stimulants: Caution should be taken when ALERTEC is used in combination with amphetamines or other similar CNS stimulants, such as methylphenidate. Some CNS stimulants may cause increases in blood pressure and heart rate, and the concomitant use of these drugs may result in additive effects. Clinically important prolongation of the QTc interval may also occur within a few hours after simultaneous administration of modafinil and dextroamphetamine. ALERTEC and other CNS stimulants should not be taken at the same time (see 9.4 Drug-Drug Interactions).
Patients Using Cyclosporine: The blood levels of cyclosporine may be reduced when used with ALERTEC (see 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions). Monitoring of circulating cyclosporine concentrations and appropriate dosage adjustment for cyclosporine should be considered when these drugs are used concomitantly.
Alcohol Consumption: The use of ALERTEC in combination with alcohol has not been studied. Pharmacodynamic interactions cannot be excluded. Patients should be advised to avoid alcohol consumption while taking ALERTEC.
Carcinogenesis and Mutagenesis
Please refer to section 16 NON-CLINICAL TOXICOLOGY for animal data.
Cardiovascular
All patients should undergo a cardiac evaluation, including an electrocardiogram (ECG), prior to ALERTEC initiation. This is particularly recommended for patients with coronary artery disease, a recent history of myocardial infarction, or unstable angina (see 4.1 Dosing Considerations).
Blood pressure and heart rate should be regularly monitored in patients receiving ALERTEC. ALERTEC should be discontinued in patients who develop arrhythmia or moderate to severe hypertension and not restarted until the condition has been adequately evaluated and treated.
The safety of ALERTEC has not been established in patients with coronary artery disease, a recent history of myocardial infarction, or unstable angina. Patients with these conditions were not included in the controlled clinical trials. Post-marketing adverse events of ischaemic heart disease, such as myocardial infarction, have been reported in patients with and without a history of cardiovascular disease while being treated with ALERTEC. In some of these cases there was a close temporal association to the use of ALERTEC. The risks of using ALERTEC in patients with coronary artery disease, a recent history of myocardial infarction, or unstable angina should be carefully weighed against the potential therapeutic benefit.
Furthermore, in clinical studies of modafinil, signs and symptoms including chest pain, palpitations, dyspnea, and transient ischemic T-wave changes on ECG were observed in three subjects in association with mitral valve prolapse or left ventricular hypertrophy. It is recommended that ALERTEC not be used in patients with a history of left ventricular hypertrophy or in patients with ischemic ECG changes, chest pain, arrhythmia, or other clinically significant manifestations of mitral valve prolapse in association with CNS stimulant use. Such signs may include but are not limited to ischemic ECG changes, chest pain, or arrhythmia. If new onset of any of these symptoms occurs, consider cardiac evaluation.
Post-marketing adverse events of cardiac arrhythmia, such as atrial fibrillation and premature ventricular contractions, have been reported in patients treated with ALERTEC. In some of these cases there was a close temporal association to the use of ALERTEC, a resolution of the arrhythmia upon drug discontinuation and, in a few cases, a recurrence of arrhythmia after ALERTEC rechallenge.
Blood pressure monitoring in short-term (<3 months) controlled trials showed no clinically significant changes in mean systolic and diastolic blood pressure in patients receiving ALERTEC compared to placebo. However, a retrospective analysis of the use of antihypertensive medication in these studies showed that a greater proportion of patients on ALERTEC required new or increased use of antihypertensive medications (2.4%) compared to patients on placebo (0.7%). The differential was slightly larger when only studies on OSA were included, with 3.4% of patients on ALERTEC and 1.1% of patients on placebo requiring such alterations in the use of antihypertensive medication.
Cardiovascular adverse reactions increase significantly after single doses of 300mg and after total daily doses of more than 400mg.
Risk of stroke: Three epidemiological studies with a common design were conducted in administrative databases assessing the cardiovascular risk of modafinil. One of the 3 studies, with a sample size best suited for detecting an effect, suggested an increase in the incidence rate of stroke in modafinil-treated patients compared to patients not treated with modafinil. Overall, a causal relationship between modafinil and stroke has not been established.
Dependence/Tolerance
The potential for abuse should be considered when prescribing ALERTEC (see 16 NON-CLINICAL TOXICOLOGY for pre-clinical results). Physicians should follow patients closely, especially those with a history of drug and/or stimulant (e.g., methylphenidate, amphetamine, or cocaine) abuse or a history of psychiatric disorders. Patients should be observed for signs of misuse (e.g., incrementation of doses or drug-seeking behavior).
In a study of 24 subjects with polysubstance abuse histories, ALERTEC doses of 200, 400, and 800mg modafinil produced psychoactive and euphoric effects, alterations in mood, perception, thinking, and feelings typical of CNS stimulants versus placebo but showed lower abuse potential relative to methylphenidate (45 and 90mg). ALERTEC did not produce a significant amphetamine score on the Addiction Research Center Inventory (ARCI) questionnaire. ALERTEC was also clearly distinguishable from amphetamine on this scale in a study of 300mg in 16 healthy volunteers. Subjective effects of ALERTEC differed markedly from those induced by 15mg of d-amphetamine, and to a lesser extent, from those seen with placebo.
Withdrawal: The effects of modafinil withdrawal were monitored following 9 weeks of modafinil use in one Phase 3 controlled clinical trial. No specific symptoms of withdrawal were observed during 14 days of observation, although sleepiness returned in narcoleptic patients.
Driving and Operating Machinery
Patients should be alerted to exercise caution when driving or operating a vehicle or potentially dangerous machinery.
There is evidence that, because of possible over-stimulation and overconfidence, ALERTEC alters the ability to perform hazardous activities in some patients. Patients should be cautioned about operating an automobile or other hazardous machinery until they are reasonably certain that ALERTEC therapy will not adversely affect their ability to engage in such activities.
Endocrine and Metabolism
ALERTEC may cause induction of hepatic microsomal enzymes, especially at doses greater than 400mg. The metabolism of oral anticoagulants, antidepressant, anticonvulsants, and oral contraceptives may be increased (see 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions). Patients should be monitored closely for changes in their response to any of these therapies when treatment with ALERTEC is either initiated or discontinued.
Hepatic/Biliary/Pancreatic
Liver Function Tests: In Phase 1, 2, and 3 studies, mean plasma levels of gamma glutamyltransferase (GGT) and alkaline phosphatase (AP) were found to be higher following administration of ALERTEC, but not placebo. Few subjects, however, had GGT or AP elevations outside of the normal range. Shifts to higher, but not clinically significantly abnormal, GGT and AP values appeared to increase with time in the population treated with ALERTEC in the Phase 3 clinical trials. No differences were apparent in alanine aminotransferase, aspartate aminotransferase, total protein, albumin, or total bilirubin.
Immune
Hypersensitivity Reactions: See 7 WARNINGS AND PRECAUTIONS, Skin for serious cutaneous adverse reactions
Angioedema and Anaphylactoid Reactions: Angioedema and anaphylactic reaction have been reported in post-marketing experience with modafinil.
One serious case of angioedema and one case of hypersensitivity (with rash, dysphagia, and bronchospasm), were observed among 1,595 patients treated in clinical trials with armodafinil (not marketed in Canada), the R-enantiomer of modafinil (which is the racemic mixture). No such cases were observed in modafinil clinical trials.
Patients should be advised to discontinue therapy and immediately report to their physician any signs or symptoms suggesting angioedema or anaphylaxis (e.g., swelling of face, eyes, lips, tongue or larynx; difficulty in swallowing or breathing; hoarseness).
Multi-organ Hypersensitivity Reactions: Multi-organ hypersensitivity reactions, including at least one fatality in post-marketing experience, have occurred in close temporal association (median time to detection 13 days: range 4-33 days) to the initiation of modafinil.
Although there have been a limited number of reports, multi-organ hypersensitivity reactions may result in hospitalization or be life-threatening. There are no factors that are known to predict the risk of occurrence or the severity of multi-organ hypersensitivity reactions associated with modafinil. Signs and symptoms of this disorder were diverse; however, patients typically, although not exclusively, presented with fever and rash associated with other organ system involvement. Other associated manifestations included myocarditis, hepatitis, liver function test abnormalities, hematological abnormalities (e.g., eosinophilia, leukopenia, thrombocytopenia), pruritus, and asthenia. Because multi-organ hypersensitivity is variable in its expression, other organ system symptoms and signs, not noted here, may occur.
If a multi-organ hypersensitivity reaction is suspected, ALERTEC should be discontinued.
Although there are no case reports to indicate cross-sensitivity with other drugs that produce this syndrome, the experience with drugs associated with multi-organ hypersensitivity would indicate this to be a possibility.
Neurologic
Central nervous system adverse reactions increase significantly after single doses of 300mg and after total daily doses of more than 400mg.
Psychiatric
Psychiatric adverse experiences have been reported in patients treated with ALERTEC. There have been reports of psychotic episodes associated with ALERTEC use. Post-marketing adverse events associated with the use of modafinil have included mania, delusions, hallucinations, and suicidal ideation and aggression, some resulting in hospitalization. Many, but not all, patients had a prior psychiatric history (see 8.1 Adverse Reaction Overview, 8.2 Clinical Trial Adverse Reactions, 8.2.1 Clinical Adverse Drug Reactions – Pediatrics, 8.5 Post-Market Adverse Reactions).
Caution should be exercised when ALERTEC is given to patients with a history of psychosis, depression, or mania. Consideration should be given to the possible emergence or exacerbation of psychiatric symptoms in patients treated with ALERTEC. If psychiatric symptoms develop in association with ALERTEC administration, consider discontinuing ALERTEC. A history of psychiatric disorders may also increase the risk of abuse or misuse of ALERTEC (see Dependence/Tolerance).
In controlled clinical trials of pediatric patients with ADHD, adverse events categorized as signs and symptoms of psychosis or mania and/or suicidal ideation were reported in <1% of patients treated with modafinil and no patients treated with placebo. Aggression and violent behavior were reported in 1% of modafinil-treated patients and no placebo-treated patients in controlled clinical trials of pediatric patients with narcolepsy or OSA. There were no reports of psychosis or mania and/or suicidal ideation in clinical trials with this pediatric population.
In the controlled and open-label clinical studies of pediatric patients with narcolepsy, treatment emergent adverse events of the psychiatric and nervous system included Tourette’s syndrome, insomnia, hostility, increased cataplexy, increased hypnagogic hallucinations and suicidal ideation.
Renal
Severe Renal Impairment: There is inadequate information to determine the safety and efficacy of dosing in patients with severe renal impairment (see 10.3 Pharmacokinetics).
Reproductive Health: Female and Male Potential
Women of childbearing potential / Contraception: ALERTEC is contraindicated in women who are pregnant or may become pregnant (see 2 CONTRAINDICATIONS, 7.1.1 Pregnant Women). Therefore, before initiation of treatment in women of childbearing potential, a negative pregnancy test must be available (see 4.1 Dosing Considerations). Women of reproductive potential should be advised to use effective contraception during therapy with modafinil and for two months after discontinuation of ALERTEC treatment (see 4.1 Dosing Considerations, 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions).
Fertility
See section 16 NON-CLINICAL TOXICOLOGY
Teratogenic Risk
Based on human data, ALERTEC is potentially teratogenic (see 2 CONTRAINDICATIONS, 7.1.1 Pregnant Women).
Skin
Severe Cutaneous Adverse Reactions: In clinical trials of modafinil, the incidence of rash resulting in discontinuation was approximately 0.8% (13 per 1,585) in pediatric patients (age <17 years); these rashes included 1 case of possible Stevens-Johnson Syndrome (SJS) and 1 case of apparent multi-organ hypersensitivity reaction (see Hypersensitivity Reactions above). Several of the cases were associated with fever and other abnormalities (e.g., vomiting, leucopenia). The median time to rash that resulted in discontinuation was 13 days. No such cases were observed among 380 pediatric patients who received placebo. No serious skin rashes have been reported in adult clinical trials (0 per 4,264) of modafinil.
Rare cases of serious or life-threatening rash, including SJS, Toxic Epidermal Necrolysis (TEN), and Drug Rash with Eosinophilia and Systemic Symptoms (DRESS), requiring hospitalisation and discontinuation of treatment, have been reported in association with the use of modafinil in adults and children in worldwide post-marketing experience (see
8.5 Post-Market Adverse Reactions).
The reporting rate of TEN and SJS associated with modafinil use, which is generally accepted to be an underestimate due to under-reporting, exceeds the background incidence rate. Estimates of the background incidence rate for these serious skin reactions in the general population range between 1 to 2 cases per million-person years.
There are no factors that are known to predict the risk of occurrence or the severity of rash associated with modafinil. Nearly all cases of serious rash associated with modafinil occurred within 1 to 5 weeks after treatment initiation. However, isolated cases have been reported after prolonged treatment (e.g., 3 months). Accordingly, duration of therapy cannot be relied upon as a means to predict the potential risk heralded by the first appearance of a rash.
Although benign rashes also occur with modafinil, it is not possible to reliably predict which rashes will prove to be serious. Accordingly, modafinil should ordinarily be discontinued at the first sign of rash, unless the rash is clearly not drug-related. Discontinuation of treatment may not prevent a rash from becoming life-threatening or permanently disabling or disfiguring.
7.1 Special Populations
7.1.1 Pregnant Women
Based on post-marketing reports, and findings from animal studies, modafinil may cause fetal harm and is contraindicated for use in women who are pregnant or may become pregnant.
If a woman becomes pregnant while taking ALERTEC, the patient must be apprised of the potential risk to the fetus.
In post-marketing reports, use of modafinil during pregnancy was associated with cases of major congenital anomalies (e.g., congenital cardiac anomalies, microcephaly). Data analyses from the ongoing Nuvigil/Provigil Pregnancy Registry in United States have documented outcomes in 133 women exposed to modafinil and/or armodafinil (the R-enantiomer of modafinil; not marketed in Canada) anytime during pregnancy or within 6 weeks prior to conception. Out of the 81 prospective pregnancy cases with a known outcome (including 5 twin pregnancies), 10 cases of spontaneous abortion were reported. Out of the 75 live births, there were 13 cases with major congenital anomalies, 3 of which were cardiac congenital anomalies. The prevalence of major congenital anomalies (17.3%) and cardiac anomalies (4.0%) for modafinil/armodafinil are above that of the general population (3% and 1% respectively). There have also been post-marketing reports of congenital malformations, small for gestational age/intrauterine growth retardation and failure to thrive in association with modafinil and armodafinil.
In studies conducted in rats and rabbits, development toxicity was observed at clinically relevant exposures. Embryotoxicity was observed in the absence of maternal toxicity when rats received oral modafinil (50, 100, or 200mg/kg/day) throughout the period of organogenesis. At a dose 5 times the maximum recommended daily human dose of 400mg on a mg/m2 basis, there was an increase in resorption, hydronephrosis and skeletal variations. The higher no-effect dose for rat embryofetal developmental toxicity was associated with a plasma modafinil exposure approximately 0.25 to 0.5 times the AUC in humans at the recommended daily dose (RHD) of 200 to 400mg. However, in a subsequent study of up to 480mg/kg/day (plasma modafinil exposure approximately 1-2 times the AUC in humans at the RHD) no adverse effects on embryofetal development were observed.
Modafinil administered orally to pregnant rabbits throughout the period of organogenesis at doses of 45, 90, and 180mg/kg/day increased the incidences of fetal structural alterations and embryofetal death at the highest dose. The highest no-effect dose for developmental toxicity was associated with a plasma modafinil AUC approximately equal to the AUC in humans at the RHD. Oral administration of armodafinil (the R-enantiomer of modafinil – not approved in Canada; 60, 200, or 600mg/kg/day) to pregnant rats throughout the period of organogenesis resulted in increased incidences of fetal visceral and skeletal variations at the intermediate dose or greater and decreased fetal body weights at the highest dose. The no-effect dose for rat embryofetal developmental toxicity was associated with a plasma armodafinil exposure (AUC) approximately one-tenth times the AUC for armodafinil in humans treated with modafinil at the RHD.
Modafinil administration to rats throughout gestation and lactation at oral doses of up to 200mg/kg/day resulted in decreased viability in the offspring at doses greater than 20mg/kg/day (plasma modafinil AUC approximately 0.05 to 0.1 times the AUC in humans at the RHD). No effects on postnatal developmental and neurobehavioral parameters were observed in surviving offspring.
7.1.2 Breast-feeding
Modafinil may be excreted in human milk. In rats, peak 14C modafinil concentrations appeared in the milk of lactating animals within one hour and at levels similar to the ones found in plasma. ALERTEC is therefore not recommended during lactation.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness in pediatric patients have not been established. ALERTEC is not approved for use in pediatric patients for any indication including Attention Deficit Hyperactivity Disorder.
In a controlled 6-week study, 165 pediatric patients (aged 5-17 years) with narcolepsy were treated with modafinil (n=123), or placebo (n=42). There were no statistically significant differences favoring modafinil over placebo in prolonging sleep latency as measured by MSLT, or in perceptions of sleepiness as determined by the Clinical Global Impression - Clinician scale (CGI-C).
7.1.4 Geriatrics
Dyskinesias have been reported in geriatric patients with the use of ALERTEC. Elimination of modafinil and its metabolites may be reduced as a consequence of aging, and geriatric patients have been found to be more sensitive to the effects of ALERTEC; these patients should be started at a lower dose (see 4.2 Recommended Dose and Dosage Adjustment, 10.3 Pharmacokinetics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most commonly observed adverse events (≥5%) associated with the use of ALERTEC and observed more frequently than placebo treated patients in the placebo controlled clinical studies in primary disorders of sleep and wakefulness were headache, nausea, rhinitis, nervousness, diarrhea, back pain, anxiety, dizziness, dyspepsia, and insomnia. The adverse event profile was similar across these studies.
In the placebo controlled clinical trials, 74 of the 934 patients (8%) who received ALERTEC discontinued due to an adverse experience compared to 3% of patients that received placebo. The most frequent reasons for discontinuation that occurred at a higher rate for ALERTEC than placebo patients were headache (2%), anxiety (1%), nervousness (1%), agitation, chest pain, confusion, depression, dizziness, insomnia, and nausea (each <1%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The following table presents the adverse experiences that occurred at a rate of 1% or more and were more frequent in adult patients treated with ALERTEC than in placebo-treated patients in the principal, placebo-controlled clinical trials.
| Table 2: Incidence of Treatment-Emergent Adverse Experiences in Parallel-Group, Placebo-controlled Clinical Trials1 with ALERTEC in Adults with Narcolepsy and Obstructive Sleep Apnea and Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder) (200mg, 300mg and 400mg)* | |||||
| Modafinil n=934 (%) | Placebo n=567 (%) | ||||
| Body as Whole | |||||
| Headache | 34% | 23% | |||
| Back Pain | 6% | 5% | |||
| Flu Syndrome | 4% | 3% | |||
| Chest Pain | 3% | 1% | |||
| Chills | 1% | 0% | |||
| Neck Rigidity | 1% | 0% | |||
| Cardiovascular | |||||
| Hypertension | 3% | 1% | |||
| Tachycardia | 2% | 1% | |||
| Palpitation | 2% | 1% | |||
| Vasodilatation | 2% | 0% | |||
| Digestive | |||||
| Nausea | 11% | 3% | |||
| Diarrhea | 6% | 5% | |||
| Dyspepsia | 5% | 4% | |||
| Dry Mouth | 4% | 2% | |||
| Anorexia | 4% | 1% | |||
| Constipation | 2% | 1% | |||
| Abnormal Liver Function2 | 2% | 1% | |||
| Flatulence | 1% | 0% | |||
| Mouth Ulceration | 1% | 0% | |||
| Thirst | 1% | 0% | |||
| Hemic/Lymphatic | |||||
| Eosiniphilia | 1% | 0% | |||
| Metabolic/Nutritional | |||||
| Edema | 1% | 0% | |||
| Nervous | |||||
| Nervousness | 7% | 3% | |||
| Insomnia | 5% | 1% | |||
| Anxiety | 5% | 1% | |||
| Dizziness | 5% | 4% | |||
| Depression | 2% | 1% | |||
| Paresthesia | 2% | 0% | |||
| Somnolence | 2% | 1% | |||
| Hypertonia | 1% | 0% | |||
| Dyskinesia3 | 1% | 0% | |||
| Hyperkinesia | 1% | 0% | |||
| Agitation | 1% | 0% | |||
| Confusion | 1% | 0% | |||
| Tremor | 1% | 0% | |||
| Table 2: Incidence of Treatment-Emergent Adverse Experiences in Parallel-Group, Placebo-controlled Clinical Trials1 with ALERTEC in Adults with Narcolepsy and Obstructive Sleep Apnea and Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder) (200mg, 300mg and 400mg)* | |||||
| Modafinil n=934 (%) | Placebo n=567 (%) | ||||
* Six double-blind, placebo controlled clinical studies in narcolepsy (200 and 400mg), OSA (200 and 400mg) and SWD (200mg and 300mg). 1 Events reported by at least 1% of patients treated with ALERTEC that were more frequent than in the placebo group are included; incidence is rounded to the nearest 1%. The adverse experience terminology is coded using a standard modified COSTART Dictionary. Events for which the ALERTEC incidence was at least 1%, but equal to or less than placebo are not listed in the table. These events included the following: abdominal pain, abnormal electrocardiogram, accidental injury, allergic reaction, arthritis, asthenia, bronchitis, cataplexy, conjunctivitis, dysmenorrhea4, dyspnea, ear pain, ecchymosis, fever, increased appetite, increased cough, infection, hyperglycemia, hypotension, hypothermia, leg cramps, migraine, myalgia, neck pain, pain, periodontal abscess, peripheral edema, rash, sinusitis, sleep disorder, thinking abnormality, tooth disorder, weight gain, weight loss, urinary tract infection, viral infection, vomiting. 2 Elevated liver enzymes. 3 Oro-facial dyskinesias. 4 Incidence adjusted for gender.
In the controlled and open-label clinical studies of pediatric patients with narcolepsy, transient leucopenia, which resolved without medical intervention, was observed. In the controlled clinical study, 3 of 38 girls, ages 12 or older, treated with modafinil experienced dysmenorrhea compared to 0 of 10 girls who received placebo. Neuropsychiatric treatment-emergent adverse events have been reported in clinical trials of pediatric patients with narcolepsy, obstructive sleep apnea (OSA) or ADHD (see 7 WARNINGS AND PRECAUTIONS, Psychiatric). Cases of serious skin reactions resulting in treatment discontinuation have been reported during clinical trials with pediatric patients (age < 17 years) (see 7 WARNINGS AND PRECAUTIONS, Skin). | |||||
| Table 2: Incidence of Treatment-Emergent Adverse Experiences in Parallel-Group, Placebo-controlled Clinical Trials1 with ALERTEC in Adults with Narcolepsy and Obstructive Sleep Apnea and Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder) (200mg, 300mg and 400mg)* | |||||
| Modafinil n=934 (%) | Placebo n=567 (%) | ||||
| Emotional Lability | 1% | 0% | |||
| Vertigo | 1% | 0% | |||
| Respiratory | |||||
| Rhinitis | 7% | 6% | |||
| Pharyngitis | 4% | 2% | |||
| Lung Disorder | 2% | 1% | |||
| Epistaxis | 1% | 0% | |||
| Asthma | 1% | 0% | |||
| Skin/Appendages | |||||
| Sweating | 1% | 0% | |||
| Herpes Simplex | 1% | 0% | |||
| Special Senses | |||||
| Amblyopia | 1% | 0% | |||
| Abnormal Vision | 1% | 0% | |||
| Taste Perversion | 1% | 0% | |||
| Eye Pain | 1% | 0% | |||
| Urogenital | |||||
| Urine Abnormality | 1% | 0% | |||
| Hematuria | 1% | 0% | |||
| Pyuria | 1% | 0% | |||
8.3 Less Common Clinical Trial Adverse Reactions
In the narcolepsy pivotal clinical trials, adverse events occurring less frequently were:
Nervous system: CNS stimulation (1.0%), and twitch (0.7%).
Skin and appendages: pruritus (1.0%).
Special senses: conjunctivitis (1.0%).
Urogenital system: urinary frequency (0.7%).
Adverse events reported only once in the narcolepsy pivotal clinical trials include:
Body as a whole: jaw pain (0.3%) and photosensitivity (0.3%).
Cardiovascular system: heart arrest (0.3%).
Digestive system: saliva increase (0.3%).
Hemic and lymphatic system: leukocytosis (0.3%).
Musculoskeletal system: myasthenia (0.3%).
Nervous system: ataxia (0.3%), coordination abnormality (0.3%), dream abnormality (0.3%), libido increase (0.3%), personality disorder (0.3%).
Special senses: decreased hearing (0.3%), hyperacusis (0.3%).
Urogenital system: cystitis (0.3%), and impotence (0.3%).
Dose Dependency of Adverse Events
In the adult placebo-controlled clinical trials which compared doses of 200, 300, and 400mg/day of ALERTEC and placebo, the only adverse events that were clearly dose related were headache and anxiety.
Vital Sign Changes: While there was no consistent change in mean values of heart rate or systolic and diastolic blood pressure, the requirement for antihypertensive medication was slightly greater in patients on ALERTEC compared to placebo.
Weight Changes: There were no clinically significant differences in body weight change in patients treated with ALERTEC compared to placebo-treated patients in the placebo-controlled clinical trials.
ECG Changes: No treatment-emergent pattern of ECG abnormalities was found in placebo-controlled clinical trials following administration of ALERTEC. In a Canadian clinical trial, a 35 year-old obese narcoleptic male with a prior history of syncopal episodes experienced a 9-second episode of asystole after 27 days of modafinil treatment (300mg/day in divided doses) (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Clinical chemistry, hematology, and urinalysis parameters were monitored in Phase 1, 2, and 3 studies. In these studies, mean plasma levels of gamma glutamyltransferase (GGT) and alkaline phosphatase (AP) were found to be higher following administration of ALERTEC, but not placebo. Few subjects, however, had GGT or AP elevations outside of the normal range. Shifts to higher, but not clinically significantly abnormal, GGT and AP values appeared to increase with time in the population treated with ALERTEC in the Phase 3 clinical trials.
No differences were apparent in alanine aminotransferase, aspartate aminotransferase, total protein, albumin, or total bilirubin.
8.5 Post-Market Adverse Reactions
In addition to the adverse events observed during clinical trials, the following adverse events have been identified during post-approval use of ALERTEC in clinical practice. Because these adverse effects are reported voluntarily from a population of uncertain size, reliable estimates of their frequency cannot be made.
Hematologic: agranulocytosis. The causality of the two cases reported could not be established due to concomitant use of Dyazide® (hydrochlorothiazide/triamterene) in the first case and of omeprazole in the second case.
Central nervous system: irritability, psychomotor hyperactivity, symptoms of mania, symptoms of psychosis
Hypersensitivity: anaphylactic reaction, angioedema, urticaria (hives)
Dermatologic: rare reports of serious skin reactions [including cases of Drug Rash with Eosinophilia and Systemic Symptoms (DRESS), erythema multiforme, Stevens-Johnson Syndrome, and Toxic Epidermal Necrolysis].
Cardiovascular: cardiac arrhythmias (including atrial fibrillation, conduction abnormalities, and premature ventricular contraction), ischaemic heart disease (including angina pectoris and myocardial infarction).
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Impact of other drugs on the metabolism of modafinil
In vitro studies using liver microsomes suggest that formation of the metabolite modafinil sulfone is primarily catalyzed by cytochrome CYP 3A. Potential inhibitors such as itraconazole or ketoconazole may therefore reduce the formation of modafinil sulfone. Because this pathway is of relatively minor importance in humans, such an interaction would not be expected to appreciably alter modafinil elimination.
Impact of modafinil on the metabolism of other drugs
Modafinil has the potential to inhibit CYP2C19, suppress CYP2C9, and induce CYP3A4, CYP2B6, and CYP1A2.
Because modafinil and modafinil sulfone are reversible inhibitors of the drug-metabolizing enzyme CYP2C19, co-administration of modafinil with drugs such as diazepam, propranolol, phenytoin, or S-mephenytoin, which are largely eliminated via that pathway, may increase the circulating levels of those compounds and may require dosage reduction and monitoring for toxicity.
The exposure of human hepatocytes to modafinil in vitro produced an apparent concentration-related suppression of expression of CYP2C9 activity suggesting that there is a potential for a metabolic interaction between modafinil and the substrates of this enzyme (e.g., S-warfarin and phenytoin).
ALERTEC has a slight induction effect at the concentration of 10-5M on CYP 3A. Chronic administration of modafinil can increase the elimination of substrates of CYP3A4. Dosage adjustment should be considered for concomitant medications that are substrates for CYP3A4, such as triazolam and cyclosporine.
In addition, in individuals deficient in the enzyme CYP2D6 (i.e., 7-10% of the Caucasian population; similar or lower in other populations), the levels of CYP2D6 substrates such as tricyclic antidepressants and selective serotonin reuptake inhibitors, which have ancillary routes of elimination through CYP2C19, may be increased by co-administration of modafinil. Dose adjustments may be necessary for patients being treated with these and similar medications.
An in vitro study demonstrated that armodafinil (one of the enantiomers of modafinil; not marketed in Canada) is a substrate of P-glycoprotein.
It should be noted that evaluation of drug interactions based on in vitro systems may not necessarily reflect those seen in vivo situations. This information should be used as a guide to assess the risks associated with the use of concomitant medications.
9.3 Drug-Behavioural Interactions
The use of ALERTEC in combination with alcohol has not been studied. Pharmacodynamic interactions cannot be excluded. Patients should be advised to avoid alcohol consumption while taking ALERTEC.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 - Established or Potential Drug-Drug Interactions
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
CNS stimulants (e.g. Methylphenidate, dextroamphetamine) | CT | Higher blood pressure, pulse rate and prolongation of the QTc interval, including a clinically important case (QTc interval = 507 msec), were observed after simultaneous administration of modafinil and dextroamphetamine. No significant alteration in the pharmacokinetics of modafinil was observed after a single administration or at steady-state. However, the absorption of modafinil may be delayed by approximately one hour when simultaneously administered with methylphenidate or dextroamphetamine. | Caution should be taken when modafinil is used in combination with amphetamines or other similar CNS stimulants. Modafinil and other CNS stimulants should not be taken at the same time. See 7 WARNINGS AND PRECAUTIONS, Cardiovascular |
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
| Clomipramine | CT | Significantly higher systolic blood pressure was observed when the two drugs were administered together (12.4 mmHg above baseline) than following administration of either drug alone (5.7 mmHg and 6.4 mmHg above baseline for modafinil and clomipramine alone, respectively). One incident of increased levels of clomipramine and its active metabolite desmethylclomipramine has been reported in a patient with narcolepsy during treatment with modafinil. | The hypertensive effects of co-administration of higher than 50mg doses of clomipramine and multiple doses of modafinil (200-400mg daily) is unknown. Therefore, caution should be exercised when co-administration of modafinil and clomipramine is deemed necessary. |
| [Proper/Common name] | Source of Evidence | Effect | Clinical comment |
CYP3A4 substrates Triazolam Ethinyl estradiol (EE2) Cyclosporine | CT C | Chronic administration of modafinil 400mg per day was found to decrease the systemic exposure to ethinyl estradiol and triazolam. Higher incidence of metrorrhagia was observed when modafinil and ethinyl estradiol were administered concomitantly. One case of an interaction between modafinil and cyclosporine has been reported. After one month of administration of 200mg/day of modafinil, cyclosporine blood levels were decreased by 50%. | Caution is recommended with the combination of oral contraceptives and modafinil. Dosage adjustment should be considered for concomitant medications that are substrates for CYP3A4, such as triazolam and cyclosporine. |
| Warfarin | CT | Chronic modafinil treatment resulted in a 20% increase in mean AUC on the single-dose pharmacokinetics of S-warfarin when compared to placebo. No changes in mean Cmax were observed. | The clinical relevance of these findings is unknown as multiple doses of warfarin were not evaluated. More frequent evaluations of prothrombin times/INR than the regular monitoring is advisable whenever modafinil is co-administered with warfarin. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Monoamine Oxidase (MAO) Inhibitors: Interaction studies with monoamine oxidase inhibitors have not been performed. Therefore, caution should be used when concomitantly administering MAO inhibitors and modafinil.
Drugs that increase blood pressure: Concomitant use of ALERTEC and other agents that may elevate blood pressure (e.g. sympathomimetics) has not been evaluated. Caution should be exercised when prescribing ALERTEC to patients already taking such agents.
Antipyrine: Multi-dose treatment (twice daily, one at 8 a.m. and one at noon) with ALERTEC at 400 mg/day or higher, for 7 days, was shown to decrease the half-life of antipyrine. This finding suggests that chronic administration of ALERTEC at 400mg or higher daily may induce the metabolism of other drugs.
CNS Active Drugs: Patients who are receiving ALERTEC with drugs with CNS activity should be monitored closely (see 7 WARNINGS AND PRECAUTIONS, General).
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Modafinil is a central nervous system stimulant.
The precise mechanism(s) through which modafinil promotes wakefulness is unknown. Modafinil has wake-promoting actions similar to sympathomimetic agents like amphetamine and methylphenidate, although the pharmacologic profile is not identical to that of sympathomimetic amines.
Modafinil-induced wakefulness can be attenuated by the α1-adrenergic receptor antagonist prazosin; however, modafinil is inactive in other in vitro assay systems known to be responsive to α-adrenergic agonists, such as the rat vas deferens preparation. Modafinil is not a direct-acting dopamine receptor agonist. However, in vitro and in vivo data indicate that modafinil binds to the dopamine transporter and inhibits dopamine reuptake. This activity has been associated in vivo with increased extracellular dopamine levels in some brain regions of animals. In genetically engineered mice lacking the dopamine transporter (DAT), modafinil lacked wake-promoting activity, suggesting that this activity was DAT-dependent). The wake-promoting effects of modafinil are antagonized by D1 and D2 receptor antagonists, suggesting that dopaminergic receptors are necessary for its activity. In addition, alpha-methyl-p-tyrosine, a dopamine synthesis inhibitor, blocks the action of dopamine, but does not block locomotor activity induced by modafinil.
Another set of experiments suggests that modafinil may act on neuronal GABAergic function by increasing the turnover rate of 5-HT and by enhancing the activity of 5-HT2 receptors. This hypothesis is supported by two sets of experiments. One shows that the acute and chronic treatment with modafinil increases significantly the levels of 5-hydroxyindolacetic acid (5-HIAA) the metabolite of 5-HT in the striatum of rats. The second set shows that modafinil inhibits the in vivo cerebral outflow of gamma aminobutyric acid (GABA) in guinea pigs and this inhibition is abolished by the pre-treatment of the animals with ketanserine, a specific 5-HT2 antagonist but not by prazosin. Hence, α-1 receptors do not appear to be involved in the inhibitory release effect of modafinil on the GABAergic function.
The following findings add to the understanding of the mechanism of action of modafinil. Prazosin reduces the level of locomotion induced by modafinil in mice but not the increased locomotion by amphetamine and methylphenidate. In the mouse, amphetamine (4mg/kg IP)
and methylphenidate (18mg/kg IP) potentiated the locomotor activity of norepinephrine given intra-ventricularly in the brain, while modafinil antagonized it. Unlike amphetamine (1-8mg/kg), modafinil at doses between 16mg and 128mg/kg IP did not cause stereotypies nor did it potentiate amphetamine-induced stereotypies in the same two species. The dose to obtain an LD50 was 6 times greater for amphetamine and 8 times greater for methylphenidate in isolated mice than in grouped mice; the dose for the LD50 of modafinil is only 1.6 times greater in isolated mice than in grouped mice. Finally, voltametric studies conducted in mice established a net difference between modafinil and amphetamine and methylphenidate. The amplitude of the oxidation peak of catecholamines recorded in the nigro-striatum remained unaffected by doses of modafinil in the range of 16 to 256mg/kg IP. Amphetamine at 2mg and 4mg/kg IP decreased the amplitude of this peak, while methylphenidate at 32 and 62mg/kg IP augmented greatly this peak.
Modafinil has weak to negligible interactions with receptors involved in the regulation of sleep/wake states (e.g., norepinephrine, serotonin, dopamine, GABA, adenosine, histamine-3, melatonin, orexin, and benzodiazepines). Modafinil also does not inhibit the activities of adenylyl cyclase, catechol-O-methyltransferase, glutamic acid decarboxylation, MAO-A or B, nitric oxide synthetase, tyrosine hydroxylase, or phosphodiesterases II-VI. Modafinil does not appear to be a direct α1-adrenoreceptor agonist. However, modafinil binds to the norepinephrine transporter and inhibits norepinephrine uptake, but these interactions are weaker than those observed with the dopamine transporter.
In addition to its wake-promoting effects and ability to increase locomotor activity in animals, modafinil has reinforcing properties, as evidenced by its self-administration in monkeys previously trained to self-administer cocaine. Modafinil was also partially discriminated as stimulant-like.
10.2 Pharmacodynamics
EEG studies in man showed that modafinil increases high frequency α waves and decreases δ and θ waves, an effect consistent with increased alertness. When taken in the evening, modafinil 200mg increases sleep latency and decreases total sleep time. Modafinil has weak peripheral sympathomimetic activity: single doses of 200mg and total daily doses of 400mg have minimal effect on hemodynamics. Higher doses cause blood pressure and heart rate to increase in a dose-dependent manner.
In addition to its wake-promoting effects and ability to increase locomotor activity in animals, modafinil in humans produces psychoactive and euphoric effects, alterations in mood, perception, thinking, and feelings typical of other CNS stimulants.
10.3 Pharmacokinetics
Modafinil is a racemic compound, whose enantiomers have different pharmacokinetics (e.g., the half-life of the l-isomer is approximately three times that of the d-isomer in adult humans). The enantiomers do not interconvert. At steady-state, total exposure to the l-isomer is approximately three times that for the d-isomer. The trough concentration (Cminss) of circulating modafinil after once daily dosing consists of 90% of the l-isomer and 10% of the d-isomer.
The effective elimination half-life of modafinil after multiple doses is about 15 hours. The enantiomers of modafinil exhibit linear kinetics upon multiple dosing of 200-600mg/day once daily in healthy volunteers. Apparent steady states of total modafinil and l-(-)-modafinil are reached after 2-4 days of dosing.
Absorption: Absorption of ALERTEC tablets is rapid, with peak plasma concentrations occurring at 2-4 hours. The bioavailability of ALERTEC tablets is approximately equal to that of an aqueous suspension. The absolute oral bioavailability was not determined due to the aqueous insolubility (<1mg/mL) of modafinil, which precluded intravenous administration.
The Cmax is slightly lower and the tmax slightly longer when ALERTEC is given after a meal but has no effect on overall ALERTEC bioavailability. Both the area under the plasma concentration curve (AUC) and the peak plasma concentration showed dose-proportionality in the 50 to 400mg range.
Distribution: Modafinil is well distributed in body tissue with an apparent volume of distribution (~0.9L/kg) larger than the volume of total body water (0.6L/kg). In human plasma, in vitro, modafinil is moderately bound to plasma protein (~60%, mainly to albumin). At serum concentrations obtained at steady state after doses of 200mg/day, modafinil exhibits no displacement of protein binding of warfarin, diazepam or propranolol. Even at much larger concentrations (1000µM; >25 times the Cmax of 40µM at steady state at 400mg/day), modafinil has no effect on warfarin binding. Modafinil acid at concentrations >500µM decreases the extent of warfarin binding, but these concentrations are >35 times those achieved therapeutically.
Metabolism and Excretion: The major route of elimination is metabolism (~90%), primarily by the liver, with subsequent renal elimination of the metabolites. Urine alkalinization has no effect on the elimination of modafinil.
Metabolism occurs through hydrolytic deamination, S-oxidation, aromatic ring hydroxylation, and glucuronic conjugation. Following oral administration of modafinil, less than 10% of the dose is found unchanged in the urine. In a clinical study using radiolabeled modafinil, a total of 81% of the administered radioactivity was recovered in 11 days post-dose, predominantly in the urine (80% vs. 1.0% in the feces). The largest fraction of the drug in urine was modafinil acid, but at least six other metabolites were present in lower concentrations. Only two metabolites reach appreciable concentrations in plasma, i.e., modafinil acid and modafinil sulfone. In preclinical models, modafinil acid, modafinil sulfone, 2-(diphenylmethyl) sulfonyl]acetic acid and 4-hydroxy modafinil, were inactive or did not appear to mediate the arousal affects of modafinil.
In adults, decreases in trough levels of modafinil have sometimes been observed after multiple weeks of dosing, suggesting auto-induction, but the magnitude of the decreases and the inconsistency of their occurrence suggest that their clinical significance is minimal. Significant accumulation of modafinil sulfone has been observed after multiple doses due to its long elimination half-life of 40 hours. Induction of metabolizing enzymes, most importantly cytochrome P-450 (CYP) 3A4, has also been observed in vitro after incubation of primary cultures of human hepatocytes with modafinil and in vivo after extended administration of modafinil at 400mg/day (see 9.2 Drug Interactions Overview and 9.4 Drug-Drug Interactions).
Special Populations and Conditions
- Sex: The pharmacokinetics of modafinil are not effected by sex.
- Age Effect: A slight decrease (∼20%) in the oral clearance (CL/F) of modafinil was observed in a single dose study at 200mg in 12 subjects with a mean age of 63 years (range 53-72 years), but the change was considered not likely to be clinically significant. In a multiple dose study (300mg/day) in 12 patients with a mean age of 82 years (range 67-87 years), the mean levels of modafinil in plasma were approximately two times those historically obtained in matched younger subjects. Due to potential effects from the multiple concomitant medications with which most of the patients were being treated, the apparent difference in modafinil pharmacokinetics may not be attributable solely to the effects of aging. However, the results suggest that the clearance of modafinil may be reduced in geriatric patients (see 4.2 Recommended Dose and Dosage Adjustment).
- Ethnic Origin: The influence of ethnic origin on the pharmacokinetics of modafinil has not been studied.
- Severe Hepatic Impairment: Pharmacokinetics and metabolism were examined in patients with cirrhosis of the liver (6 males and 3 females). Three patients had stage B or B+ cirrhosis (per the Child criteria) and 6 patients had stage C or C+ cirrhosis. Clinically 8 of 9 patients were icteric and all had ascites. In these patients, the oral clearance of modafinil was decreased by about 60% and the steady state concentration was doubled compared to normal patients. The dose of ALERTEC should be reduced in patients with hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment).
- Renal Impairment: In a single dose 200mg modafinil study, severe chronic renal failure (creatinine clearance ≤ 20mL/min) did not significantly influence the pharmacokinetics of modafinil, but exposure to modafinil acid (an active metabolite) was increased 9-fold. No adverse events were reported in this small number of patients. The clinical significance of increased modafinil acid plasma concentrations is unknown.
11 STORAGE, STABILITY AND DISPOSAL
Store between 15° and 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
This information is not available for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Modafinil
Chemical name: 2-[(diphenylmethyl)sulphinyl] acetamide
Molecular formula and molecular mass: C15H15NO2 S 273.35
Structural formula:
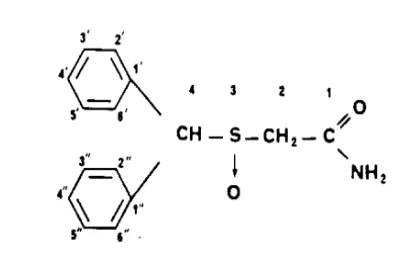
Physicochemical properties: Practically insoluble in water; sparingly soluble in acetone and methanol, slightly soluble in ethanol and chloroform.
Melting Point: 162°C
Physical Form: White crystalline powder
14 CLINICAL TRIALS
The effectiveness of ALERTEC in reducing excessive sleepiness has been established in the following sleep disorders: narcolepsy, obstructive sleep apnea (OSA) and circadian rhythm sleep disorder, sleep work type (shift work disorder) (SWD).
14.1 Clinical Trials by Indication
Narcolepsy
The effectiveness of ALERTEC in reducing the excessive sleepiness (ES) associated with narcolepsy was established in two 9-week, multicenter, placebo-controlled, two-dose (200mg per day and 400mg per day) parallel-group, double-blind studies of outpatients who met the ICD-9 and American Sleep Disorders Association criteria for narcolepsy (which are also consistent with the American Psychiatric Association DSM-IV criteria). These criteria include either 1) recurrent daytime naps or lapses into sleep that occur almost daily for at least three months, plus sudden bilateral loss of postural muscle tone in association with intense emotion (cataplexy) or 2) a complaint of excessive sleepiness or sudden muscle weakness with associated features: sleep paralysis, hypnagogic hallucinations, automatic behaviors, disrupted major sleep episode; and polysomnography demonstrating one of the following: sleep latency less than 10 minutes or rapid eye movement (REM) sleep latency less than
20 minutes. In addition, for entry into these studies, all patients were required to have objectively documented excessive daytime sleepiness, a Multiple Sleep Latency Test (MSLT) with two or more sleep onset REM periods, and the absence of any other clinically significant active medical or psychiatric disorder. The MSLT, an objective daytime polysomnographic assessment of the patient’s ability to fall asleep in an unstimulating environment, measures latency (in minutes) to sleep onset averaged over 4 test sessions at 2-hour intervals following nocturnal polysomnography. For each test session, the subject was told to lie quietly and attempt to sleep. Each test session was terminated after 20 minutes if no sleep occurred or 15 minutes after sleep onset.
In both studies, the primary measures of effectiveness were 1) sleep latency, as assessed by the Maintenance of Wakefulness Test (MWT) and 2) the change in the patient’s overall disease status, as measured by the Clinical Global Impression of Change (CGI-C). For a successful trial, both measures had to show significant improvement.
The MWT measures latency (in minutes) to sleep onset averaged over 4 test sessions at 2-hour intervals following nocturnal polysomnography. For each test session, the subject was asked to attempt to remain awake without using extraordinary measures. Each test session was terminated after 20 minutes if no sleep occurred or 10 minutes after sleep onset. The CGI-C is a 7-point scale, centered at No Change, and ranging from Very Much Worse to Very Much Improved. Patients were rated by evaluators who had no access to any data about the patients other than a measure of their baseline severity. Evaluators were not given any specific guidance about the criteria they were to apply when rating patients.
Other assessments of effect included the Multiple Sleep Latency Test (MSLT), Epworth Sleepiness Scale (ESS; a series of questions designed to assess the degree of sleepiness in everyday situations) the Steer Clear Performance Test (SCPT; a computer-based evaluation of a patient’s ability to avoid hitting obstacles in a simulated driving situation), standard nocturnal polysomnography, and patient’s daily sleep log. Patients were also assessed with the Quality of Life in Narcolepsy (QOLIN) scale, which contains the validated SF-36 health questionnaire.
Both studies demonstrated improvement in objective and subjective measures of excessive daytime sleepiness for both the 200mg and 400mg doses compared to placebo. Patients treated with either dose of ALERTEC showed a statistically significantly enhanced ability to remain awake on the MWT (all p values <0.00l) at Weeks 3, 6, 9, and final visit compared to placebo and a statistically significantly greater global improvement, as rated on the CGI-C scale (all p values <0.05).
The average sleep latencies (in minutes) on the MWT at baseline for the 2 controlled trials are shown in Table 4 below, along with the average change from baseline on the MWT at final visit.
The percentages of patients who showed any degree of improvement on the CGI-C in the two clinical trials are shown in Table 5 below.
Similar statistically significant treatment-related improvements were seen on other measures of impairment in narcolepsy, including a patient assessed level of daytime sleepiness on the ESS (p<0.001 for each dose in comparison to placebo).
Nighttime sleep measured with polysomnography was not affected by the use of ALERTEC.
Obstructive Sleep Apnea (OSA)
The effectiveness of ALERTEC in reducing the excessive sleepiness associated with OSA was established in two clinical trials. In both studies, patients were enrolled who met the International Classification of Sleep Disorders (ICSD) criteria for OSA (which are also consistent with the American Psychiatric Association DSM-IV criteria). These criteria include either, 1) excessive sleepiness or insomnia, plus frequent episodes of impaired breathing during sleep, and associated features such as loud snoring, morning headaches and dry mouth upon awakening; or 2) excessive sleepiness or insomnia and polysomnography demonstrating one of the following: more than five obstructive apneas, each greater than 10 seconds in duration, per hour of sleep and one or more of the following: frequent arousals from sleep associated with the apneas, bradytachycardia, and arterial oxygen desaturation in association with the apneas. In addition, for entry into these studies, all patients were required to have excessive sleepiness as demonstrated by a score ≥10 on the Epworth Sleepiness Scale, despite treatment with continuous positive airway pressure (CPAP). Evidence that CPAP was effective in reducing episodes of apnea/hypopnea was required along with documentation of CPAP use.
In the first study, a 12-week multicenter placebo-controlled trial, a total of 327 patients were randomized to receive ALERTEC 200mg/day, ALERTEC 400mg/day, or matching placebo. The majority of patients (80%) were fully compliant with CPAP, defined as CPAP use >4 hours/night on >70% nights. The remainder were partially CPAP compliant, defined as CPAP use <4 hours/night on >30% nights. CPAP use continued throughout the study. The primary measures of effectiveness were 1) sleep latency, as assessed by the Maintenance of Wakefulness Test (MWT) and 2) the change in the patient’s overall disease status, as measured by the Clinical Global Impression of Change (CGI-C) at Week 12 or the final visit.
Patients treated with ALERTEC showed a statistically significant improvement in the ability to remain awake compared to placebo-treated patients as measured by the MWT (p<0.001) at endpoint [Table ]. ALERTEC-treated patients also showed a statistically significant improvement in clinical condition as rated by the CGI-C scale (p<0.001) [Table 5]. The two doses of ALERTEC performed similarly.
In the second study, a 4-week multicenter placebo-controlled trial, 157 patients were randomized to either ALERTEC 400mg/day or placebo. Documentation of regular CPAP use (at least 4 hours/night on 70% of nights) was required for all patients.
The primary outcome measure was the change from baseline on the ESS at Week 4 or final visit. The baseline ESS scores for the ALERTEC and placebo groups were 14.2 and 14.4, respectively. At Week 4, the ESS was reduced by 4.6 in the ALERTEC group and by 2.0 in the placebo group, a difference that was statistically significant (p<0.0001).
Nighttime sleep measured with polysomnography was not affected by the use of ALERTEC.
Circadian Rhythm Sleep Disorder, Shift Work Type (Shift Work Disorder) (SWD)
The effectiveness of ALERTEC for the excessive sleepiness associated with SWD was demonstrated in a 12-week placebo-controlled clinical trial. A total of 209 patients with chronic SWD were randomized to receive ALERTEC 200mg/day or placebo. All patients met the International Classification of Sleep Disorders (ICSD-10) criteria for chronic SWD (which are consistent with the American Psychiatric Association DSM-IV criteria for Circadian Rhythm Sleep Disorder: Shift Work Type). These criteria include 1) either: a) a primary complaint of excessive sleepiness or insomnia which is temporally associated with a work period (usually night work) that occurs during the habitual sleep phase, or b) polysomnography and the MSLT demonstrate loss of a normal sleep-wake pattern (i.e., disturbed chronobiological rhythmicity); and 2) no other medical or mental disorder accounts for the symptoms, and 3) the symptoms do not meet criteria for any other sleep disorder producing insomnia or excessive sleepiness.
It should be noted that not all patients with a complaint of sleepiness who are also engaged in shift work meet the criteria for the diagnosis of SWD. In the clinical trial, only patients who were symptomatic for at least 3 months were enrolled.
Enrolled patients were also required to work a minimum of 5 night shifts per month, have excessive sleepiness at the time of their night shifts (MSLT score <6 minutes), and have daytime insomnia documented by a daytime polysomnogram (PSG).
The primary measures of effectiveness were 1) sleep latency, as assessed by the Multiple Sleep Latency Test (MSLT) performed during a simulated night shift at Week 12 or the final visit and 2) the change in the patient’s overall disease status, as measured by the Clinical Global Impression of Change (CGI-C) at Week 12 or the final visit. Patients treated with ALERTEC showed a statistically significant prolongation in the time to sleep onset compared to placebo-treated patients, as measured by the night-time MSLT (p<0.05). Improvement on the CGI-C was also observed to be statistically significant (p<0.001).
Daytime sleep measured with polysomnography was not affected by the use of ALERTEC.
| Table 4: Average Baseline Sleep Latency and Change from Baseline at Final Visit in Adults (MWT and MSLT in minutes) | |||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Disorder | Measure | ALERTEC 200mg* | ALERTEC 400mg* | Placebo | |||||||||||||||
| Baseline | Change from Baseline | Baseline | Change from Baseline | Baseline | Change from Baseline | ||||||||||||||
| Narcolepsy I | MWT | 5.8 | 2.3 | 6.6 | 2.3 | 5.8 | -0.7 | ||||||||||||
| Narcolepsy II | MWT | 6.1 | 2.2 | 5.9 | 2.0 | 6.0 | -0.7 | ||||||||||||
| OSA | MWT | 13.1 | 1.6 | 13.6 | 1.5 | 13.8 | -1.1 | ||||||||||||
| SWD | MSLT | 2.1 | 1.7 | - | - | 2.0 | 0.3 | ||||||||||||
| * Significantly different than placebo for all trials (p<0.01 for all trials but SWD, which was p<0.05) | |||||||||||||||||||
| Table 5: Clinical Global Impression of Change (CGI-C) (Percent of Adult Patients Who Improved at Final Visit) | ||||||||
|---|---|---|---|---|---|---|---|---|
| Disorder | ALERTEC 200mg* | ALERTEC 400mg* | Placebo | |||||
| Narcolepsy I | 64 % | 72 % | 37 % | |||||
| Narcolepsy II | 58 % | 60 % | 38 % | |||||
| OSA | 61 % | 68 % | 37 % | |||||
| SWD | 74 % | - | 36 % | |||||
| * Significantly different than placebo for all trials (p<0.01) | ||||||||
14.2 Comparative Bioavailability Study
A randomized crossover comparative bioavailability study was performed on twenty-four (24) healthy adult male volunteers under fasting conditions to evaluate a change in formulation of ALERTEC with changes in the nonmedicinal ingredients (with or without magnesium monosilicate). The results from measured data following a single administration of a 200mg dose (2 x100mg tablets) of test and reference products are summarized in Table 6.
| Table 6: Modafinil (2 x 100mg) From Measured Data – Healthy Subjects Under Fasting Conditions | |||||||
|---|---|---|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval of Ratio of Geometric Means | |||
AUCT (µg•hr/mL) | 52.0# 53.5 (24.6) € | 53.8# 55.4 (24.7) € | 96.6 | (93.0; 100.3) | |||
AUCI (µg•hr/mL) | 56.4# 58.1 (25.5) € | 58.5# 60.4 (26.1) € | 96.3 | (93.2; 99.4) | |||
CMAX (µg/mL) | 4.5# 4.6 (20.5) € | 4.5# 4.6 (17.4) € | 98.7 | (93.0; 104.8) | |||
TMAX§ (h) | 2.0 (0.5, 4) | 2.0 (0.5, 4) | |||||
T½φ (h) | 12.4 (3.00) | 13.5 (3.73) | |||||
* Tablets formulated without magnesium monosilicate.
† Tablets formulated with magnesium monosilicate.
# Expressed as the geometric mean.
€ Expressed as the arithmetic mean (Coefficient of Variation % - CV% )
§ Expressed as median (range).
φ Expressed as the arithmetic mean (Standard Deviation - SD).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Detailed Pharmacology
Increased Wakefulness
The administration of modafinil increases the spontaneous locomotor activity after single or repeated dosing in animals. After oral or intraperitoneal administration in mice, modafinil induced an increase of 45% (16mg/kg) to 173% (256mg/kg) in locomotion after one hour. No agitation, stereotypy, or convulsions were observed. The intensity and duration of action of the increased locomotion, were directly related to the blood concentration of modafinil. Repeat oral administration from 4 to 18 days maintained the induction of hyperactivity of the animals; this effect however could be reduced by up to 25% due to the liver enzymatic induction caused by modafinil.
The modafinil "increased wakefulness" can also be shown in other mouse models. In the behavioral despair test, modafinil progressively decreased the duration of immobilization from 45% (8mg/kg IP) to 95% (128mg/kg IP). Modafinil reduced the duration of sleep induced by barbital. A reduction in sleep duration of 47% and 78% was recorded in mice treated with 16mg and 64mg/kg of barbital respectively. A similar reduction was seen with chloral hydrate but not with pentobarbital or methaqualon.
The "increased wakefulness" by modafinil is not only documented in mice but also in rats, monkeys, and cats. In rats, locomotor hyperactivity appeared at intraperitoneal doses equal to or greater than 32mg/kg. Over a period of 12 hours, locomotion in monkeys increased after a single dose from 68% (16mg/kg) to 880% when modafinil was given orally (64mg/kg). The percentage of wakefulness was also altered by modafinil in this species. At the single oral dose of 3, 6, and 12mg/kg, modafinil increased the wakefulness time by 21%, 160%, and 298% respectively. In the cat at the oral dose of 5mg/kg, modafinil increased the wakefulness and delayed the appearance of the slow wave and REM sleep phases.
In non-clinical models, equal wakefulness-promoting doses of methylphenidate and amphetamine increase neuronal activation throughout the brain, whereas modafinil, unlike classical psychomotor stimulants, predominantly affects brain regions implicated in regulating arousal, sleep, wake and vigilance.
General Pharmacology
In genetically hypertensive rats, or in conscious or anaesthetized dogs, modafinil at intraduodenal doses of between 100 to 200mg/kg induced practically no effect on the cardiovascular and respiratory systems. Modafinil reduced moderately the induced hypertensive effect by amines such as epinephrine, tyramine, but essentially left intact the induced hypotensive effect by agents such as acetylcholine, histamine, and angiotensin in anaesthetized dogs. After single doses of between 100 and 200mg/kg orally, modafinil did not alter urinary excretion, biliary secretion, pancreatic secretion, or peristaltic waves in dogs and rats. Finally, modafinil in Swiss mice had a stimulating effect on T cells at 1mg/kg, a slight stimulating effect on humoral immunity but no effect on cellular immunity.
Toxicology
General Toxicology
Acute toxicity
Acute toxicity studies were conducted with modafinil in the mouse, rat and dog. At high doses, all three species displayed hyperlocomotion and stereotypy movements. In mice and rats, mortality was delayed between Day 1 and Day 9. The following symptoms were observed in dogs at single doses of 200mg/kg and 400mg/kg: tachycardia, tachypnea, hyperthermia, moderate mydriosis during the stimulation phase, and delayed vomiting.
| Species | Route | Sex | LD50 ± SD, mg/kg At 2 weeks | 95% confidence Limits mg/kg |
|---|---|---|---|---|
| Mouse | PO IP | M + F M + F | 1,370 ± 93 792 ± 61 | 1,208 - 1,562 682 - 919 |
| Rat | PO IP F | M F M 2,300 ± 293 | 2,000 ± 330 1,600 ± 222 1,400 ± 179 1,811 - 2,921 | 1,504 - 2,660 1,270 - 2,016 1,102 - 1,778 |
In the Beagle dog the oral lethal dose was between 300 and 400mg/kg.
Long-Term Toxicity
The toxicity of modafinil was initially evaluated in rats for a period of up to 3 months. After daily oral administration for 3 months of 50mg/kg, modafinil was relatively well tolerated. A slight anemia was observed, with hemosiderosis of the spleen, and a moderate increase of blood cholesterol. At higher doses, hepatomegalia without histological consequences appeared (100mg/kg) as well as an increase in the weight of kidneys and spleen (200mg/kg). The phenomena observed were reversible or in the process of reversibility two weeks after treatment discontinuation.
The toxicity of modafinil given orally was further evaluated in a 26-week study in rats. At the end of 26 weeks at the maximum dose of 200mg/kg the main change was an increase in liver weight (+18%) in males which appears to be due to enzymatic induction. Cholesterol levels, and the weight of the kidney and of the spleen were slightly increased in males.
The toxicity of modafinil was also examined via the oral route in Beagle dogs for twelve weeks at doses of 20, 50 and 75mg/kg/day. At the dose of 20mg/kg increase in serum cholesterol and alkaline phosphatase levels were seen. These changes were not associated with any histological alteration of the liver or of the other organs. At doses of 50 and 75mg/kg/day the same effects were present with a decrease in appetite and a weight loss. Although the increase was not statistically significant, weight of the liver, adrenals, and thyroid glands were increased. Enzymatic induction may explain the increased liver weight; and stress may have caused the increased adrenal weight. The histological examination did not detect any systematic treatment-related abnormality.
A 52-week study in the treated Beagle dog was also conducted with an oral dose of 10 to 40mg/kg/day. Animals receiving 20 or 40mg/kg/day had a significant increase in the weight of their liver and kidneys when compared to controls. No morphological changes were seen to account for the weight changes in the liver and kidneys at autopsy.
Carcinogenicity
The potential carcinogenicity of modafinil was tested in mice for 78 weeks and in rats for 104 weeks at an oral daily dose of 6, 30, and 60mg/kg/day. The highest dose studied is 0.75 to 1.5 (mouse) or 1.5 to 3 (rat) times greater than the recommended adult human daily dose of modafinil (200 to 400mg) on a mg/m2 basis. At 60mg/kg/day (mouse) modafinil induced an increase in liver weight in line with a hepatocellular hypertrophy. Modafinil did not show carcinogenic potential nor did it cause an increase in spontaneously occurring tumors. The 60mg/kg/day (rat) male group had a statistically higher mortality rate than control groups. The mortality was associated with a higher incidence of moderate and chronic severe nephropathies which were probably treatment-related. The most severe renal lesions correlated also with significant higher levels of serum calcium, urea and cholesterol. There were no treatment-related changes in the 6mg/kg/day. The result of this study showed no evidence of any treatment-related disturbance of the normally expected spontaneous tumor profile of the Sprague-Dawley rat.
However, since the mouse study used an inadequate high dose that was not representative of a maximum tolerated dose, a subsequent carcinogenicity study was conducted in the Tg.AC transgenic mouse. Doses evaluated in the Tg.AC assay were 125, 250 and 500mg/kg/day, administered dermally. There was no evidence of tumorigenicity associated with modafinil administration; however, this dermal model may not adequately assess the carcinogenic potential of an orally administered drug.
Genotoxicity
Modafinil demonstrated no evidence of mutagenic or clastogenic potential in a series of in vitro (i.e., bacterial reverse mutation assay, mouse lymphoma tk assay, chromosomal aberration assay in human lymphocytes cell transformation assay in BALB/3T3 mouse embryo cells) assays in the absence or presence of metabolic activation, or in vivo (mouse bone marrow micronucleus) assays. Modafinil was also negative in the unscheduled DNA synthesis assay in rat hepatocytes.
Reproductive and Developmental Toxicology
Fertility and General Reproduction Capacity: Oral administration of modafinil (doses of up to 480mg/kg/day) to male and female rats prior to and throughout mating, and continuing in females through Day 7 of gestation produced an increase in the time to mate at the highest dose; no effects were observed on other fertility or reproductive parameters. The no-effect dose of 240mg/kg/day was associated with a plasma modafinil exposure (AUC) approximately equal to that in humans at the dose of 200mg.
Assessment of Embryotoxicity: see 7.1.1 Pregnant Women
Perinatal and Postnatal Toxicity Study: At oral doses of 20, 50 and 100mg/kg/day in the rat, modafinil induced no perinatal or postnatal toxicity.
Special Toxicology
Dependence Liability
Several animal models with rats and monkeys were used to evaluate the dependence liability of modafinil. In the discrimination model, cocaine-trained rats could not differentiate between 3 to 100mg/kg of modafinil and saline. It was only at the maximum tested dose of 250mg/kg that modafinil could substitute for cocaine. In this test, modafinil is approximately 250 times less potent than amphetamine and about 15 times less potent than 1-ephedrine. In a second discriminate test, in which rats were trained to discriminate amphetamine from vehicle, modafinil showed no ability to produce an amphetamine-like effect except at a toxic dose of 250mg/kg. In another test, 91% of rats took an average of 35 sessions to acquire the discrimination of 1mg/kg of amphetamine (1mg/kg). By contrast, after an average of 69 sessions only 41% of the animals could discriminate modafinil at the dose of 64mg/kg. With the conditioned place preference test in rats, amphetamine 2mg/kg induced a clear cut place preference while modafinil at doses between 16 to 128mg/kg failed to do so. In an intravenous self-administration paradigm conducted with rats, modafinil (0.1 to 0.6mg/injection) did not act as a positive reinforcer when compared to cocaine (0.275mg/injection). Finally, in the self-administration test conducted in cocaine-trained monkeys, intravenous infusion of low dose (0.03mg/kg/injection) modafinil was not a substitute for cocaine. At a higher infusion dose of modafinil (0.1 and 0.3mg/kg/injection), the number of self-administrations increased above the number of administrations with the vehicle with a total average modafinil dose ranging from 0.4 to 34.7mg/kg per 1-hour session. When compared to l-ephedrine in the same experimental model, modafinil appear to be at least 3 times less potent than l-ephedrine.