


Product Monograph - Quillivant ER Chewable Tablets
Recent Major Label Changes
| 7 Warnings and Precautions, Endocrine and Metabolism, Long-term Suppression of Growth | 2026-02 |
|---|---|
| 7 Warnings and Precautions, 7.1.3 Pediatrics, Pediatrics (<6 years of age) | 2026-02 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ................................................................................................... 2
Table of Contents ................................................................................................................... 2
Part 1: Healthcare Professional Information ........................................................................... 4
1 Indications .................................................................................................................. 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 Contraindications ........................................................................................................ 5
3 Serious Warnings and Precautions Box ....................................................................... 5
4 Dosage and Administration ......................................................................................... 5
4.1 Dosing Considerations .......................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ..................................................... 6
4.3 Reconstitution ...................................................................................................... 7
4.4 Administration ...................................................................................................... 7
4.5 Missed Dose ......................................................................................................... 8
5 Overdose..................................................................................................................... 8
6 Dosage Forms, Strengths, Composition, and Packaging ............................................... 8
7 Warnings and Precautions ........................................................................................... 9
7.1 Special Populations ............................................................................................. 14
7.1.1 Pregnancy ....................................................................................................... 14
7.1.2 Breastfeeding ................................................................................................. 15
7.1.3 Pediatrics ........................................................................................................ 15
7.1.4 Geriatrics ........................................................................................................ 15
8 Adverse Reactions ..................................................................................................... 16
8.1 Adverse Reaction Overview ................................................................................ 16
8.2 Clinical Trial Adverse Reactions .......................................................................... 16
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................... 16
8.5 Post-Market Adverse Reactions ......................................................................... 20
9 Drug Interactions ...................................................................................................... 22
9.1 Serious Drug Interactions ................................................................................... 22
9.2 Drug Interactions Overview ................................................................................ 22
9.3 Drug-Behaviour Interactions .............................................................................. 22
9.4 Drug-Drug Interactions ....................................................................................... 23
9.5 Drug-Food Interactions ....................................................................................... 24
9.6 Drug-Herb Interactions ....................................................................................... 24
9.7 Drug-Laboratory Test Interactions ...................................................................... 24
10 Clinical Pharmacology ............................................................................................... 24
10.1 Mechanism of Action .......................................................................................... 24
10.2 Pharmacodynamics ............................................................................................ 24
10.3 Pharmacokinetics ............................................................................................... 25
11 Storage, Stability, and Disposal ................................................................................. 28
Part 2 : Scientific Information ............................................................................................... 29
13 Pharmaceutical Information ...................................................................................... 29
14 Clinical Trials ............................................................................................................. 29
14.1 Clinical Trials by Indication ................................................................................. 30
15 Non-Clinical Toxicology ............................................................................................. 33
Patient Medication Information ........................................................................................... 35
Patient Medication Information ........................................................................................... 46
Part 1: Healthcare Professional Information
1 Indications
Quillivant ER Oral Suspension (methylphenidate hydrochloride extended-release powder for oral suspension) is indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in:
- Children (6-12 years of age)
Quillivant ER Chewable Tablets (methylphenidate hydrochloride extended-release chewable tablets) are indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in:
- Children (6-12 years of age)
Long-Term Use
The effectiveness of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets for long-term use has not been systematically evaluated for more than two weeks and 1 week, respectively, in placebo-controlled trials. Therefore, the healthcare professional who elects to use Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets for extended periods should periodically re-evaluate the long-term usefulness of the drug for the individual patient (see 4 Dosage and Administration).
Need for Comprehensive Treatment Program
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are indicated as an integral part of a total treatment program for ADHD that may include other measures (psychological, educational, social) for patients with this syndrome. Drug treatment may not be indicated for all patients with this syndrome. Drug treatment is not intended for use in the patient who exhibits symptoms secondary to environmental factors and/or other primary psychiatric disorders, including psychosis. Appropriate educational placement is essential in children and adolescents with this diagnosis and psychosocial intervention is often helpful. When remedial measures alone are insufficient, the decision to prescribe drug treatment medication will depend upon the healthcare professional’s assessment of the chronicity and severity of the patient’s symptoms.
1.1 Pediatrics
Pediatrics (< 6 years of age): Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should not be used in children under six years. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use in patients under 6 years of age.
Pediatrics (6-12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in pediatric patients aged 6-12 years has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 4.2 Recommended Dose and Dosage Adjustment).
Pediatrics (13-17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in pediatric patients aged 13-17 years has not been established; therefore, Health Canada has not authorized an indication for use in ages 13-17 years.
1.2 Geriatrics
Geriatrics (>65 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2 Contraindications
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with other methylphenidate products (see 8 Adverse Reactions). For a complete listing, see 6 Dosage forms, Strengths, Composition, and Packaging. Additionally, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are contraindicated in patients with the following:
- Known hypersensitivity or idiosyncrasy to the sympathomimetic amines
- Thyrotoxicosis
- Advanced arteriosclerosis
- Symptomatic cardiovascular disease
- Moderate to severe hypertension
- Glaucoma
- History of drug abuse
- During or within 14-days following the administration of monoamine oxidase inhibitors (hypertensive crises may result) (see 9 Drug Interactions).
3 Serious Warnings and Precautions Box
- Drug Dependence – Like other stimulants, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets have the potential to be abused, leading to dependence and tolerance (see 7 Warnings and Precautions, Dependence, Tolerance, and/or Abuse Liability).
4 Dosage and Administration
4.1 Dosing Considerations
- Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should not be used in patients with symptomatic cardiovascular disease and should generally not be used in patients with known structural cardiac abnormalities (see 2 Contraindications and 7 Warnings and Precautions, Cardiovascular).
- Theoretically, there exists a pharmacological potential for all ADHD drugs to increase the risk of sudden/cardiac death. Although confirmation of an incremental risk for adverse cardiac events arising from treatment with ADHD medications is lacking, prescribers should consider this potential risk.
- Prior to treating children with CNS stimulants including Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets, assess for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) (see 7 Warnings and Precautions).
Assess the risk of abuse prior to prescribing and monitor for signs of abuse and dependence while
- on therapy. Maintain careful prescription records, educate patients about abuse, monitor for signs of abuse and overdose, and periodically re-evaluate the need for Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets use (see 3 Serious Warnings and Precautions Box, 7 Warnings and Precautions, Dependence, Tolerance and/or Abuse Liability).
- Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be administered starting at the lowest possible dose. Dosage should then be individually and slowly adjusted to the lowest effective dosage since individual patient response to Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets varies widely (see 4.2 Recommended Dose and Dosage Adjustment).
- If paradoxical aggravation of symptoms or other adverse effects occur, reduce dosage, or, if necessary, discontinue the drug. Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be periodically discontinued to assess the child's condition. If improvement is not observed after appropriate dosage adjustment over a one-month period, the drug should be discontinued.
- Pharmacologic treatment of ADHD may be needed for extended periods. Health care providers should periodically re-evaluate the long-term use of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets, and adjust dosage as needed.
- Patients who are considered to need extended treatment with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should undergo periodic evaluation of their cardiovascular status (see 7 Warnings and Precautions, Cardiovascular).
- Patients should be advised to avoid alcohol while taking Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets.
- Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are not interchangeable (see 4.2 Recommended Dose and Dosage Adjustment).
4.2 Recommended Dose and Dosage Adjustment
Quillivant ER Oral Suspension:
- Before administering the dose, VIGOROUSLY SHAKE the bottle of Quillivant ER Oral Suspension for at least 10 seconds, to ensure that the proper dose is administered.
- The recommended starting dose of Quillivant ER Oral Suspension for patients 6-12 years is 20 mg once daily in the morning. The dose may be titrated up or down weekly in increments of 10 mg or 20 mg. Daily doses above 60 mg have not been studied and are not recommended. As with any CNS stimulant, during titration of Quillivant ER Oral Suspension, the prescribed dose should be adjusted, if necessary, until a well-tolerated, therapeutic dose is achieved.
- Patients that are unable to tolerate the minimum dose of 20 mg should not take this medication.
Quillivant ER Chewable Tablets:
- The recommended starting dose of Quillivant ER Chewable Tablets for patients 6-12 years is 20 mg once daily orally in the morning. The dose may be titrated up or down weekly in increments of 10 mg, 15 mg, or 20 mg. The 10 mg and 15 mg doses can each be achieved by breaking in half the functionally scored 20 mg and 30 mg tablets, respectively. Daily doses above 60 mg have not been studied and are not recommended. As with any CNS stimulant, during titration of Quillivant ER Chewable Tablets, the prescribed dose should be adjusted, if necessary, until a well-tolerated, therapeutic dose is achieved.
- Patients that are unable to tolerate the minimum dose of 20 mg should not take this medication.
If switching from other methylphenidate products, including switching from Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets or vice versa, discontinue that treatment, and titrate with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets using the above titration schedule.
Do not substitute for other methylphenidate products on a milligram-per-milligram basis, because of different methylphenidate base compositions and differing pharmacokinetic profiles (see 10 Clinical Pharmacology).
4.3 Reconstitution
Quillivant ER Oral Suspension is supplied as a powder for oral suspension which must be reconstituted with water by the pharmacist prior to dispensing. Preparation instructions: Tap bottle until powder flows freely. Remove bottle cap and add specified amount of water to the bottle (see
Table 1). Fully insert bottle adapter into neck of bottle (Figure 1). Replace bottle cap. Shake with vigorous back and forth motion for at least 10 seconds to prepare suspension.
Figure 1: Bottle Adapter Insertion
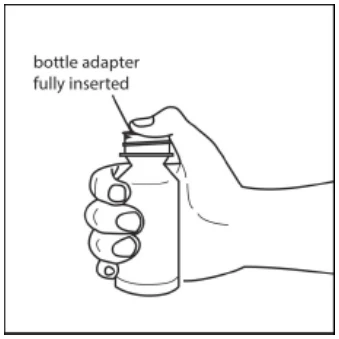
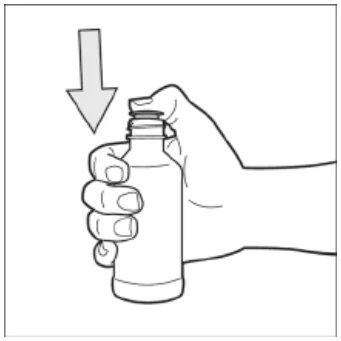
Table 1: Quillivant ER Oral Suspension Product Reconstitution Instructions - 5 mg/mL
| Amount of drug in bottle | Amount of water to add to bottle | Final reconstituted volume (yield) |
| 300 mg | 53 mL | 60 mL |
| 600 mg | 105 mL | 120 mL |
| 750 mg | 131 mL | 150 mL |
| 900 mg | 158 mL | 180 mL |
Store reconstituted Quillivant ER Oral Suspension at 15 to 30°C. Dispense in original packaging (bottle in carton) with bottle adapter inserted and with enclosed oral dosing dispenser. Quillivant ER Oral Suspension is stable for up to 4 months after reconstitution.
4.4 Administration
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be orally administered once daily in the morning with or without food (see 10 Clinical Pharmacology).
4.5 Missed Dose
If a dose of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets is missed, the patient should be instructed to take the next dose in the usual amount at the usual time the next morning. Patients should be instructed not to take an afternoon dose and not to double the dose.
5 Overdose
Signs and symptoms of acute methylphenidate overdose, resulting principally from overstimulation of the CNS and from excessive sympathomimetic effects, may include the following: agitation, cardiac arrhythmias, confusion, convulsions (may be followed by coma), delirium, euphoria, flushing, hallucinations, headache, hyperpyrexia, hyperreflexia, hypertension, muscle twitching, mydriasis and dryness of mucus membranes, rhabdomyolysis, palpitations, sweating, tachycardia, tremors and vomiting.
Management consists of providing supportive measures. The patient must be protected against self-injury and against external stimuli that would exacerbate overstimulation already present. Intensive care must be provided to maintain adequate circulation and respiratory exchange. External cooling procedures may be required to reduce hyperpyrexia. Efficacy of peritoneal dialysis or extracorporeal hemodialysis for methylphenidate overdose has not been established. The prolonged release of methylphenidate from Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be considered when treating patients with overdose. Alcohol may induce the production of methylphenidate. The amount of methylphenidate production is proportional to the blood alcohol concentration (see 9.2 Drug Interactions Overview). As with the management of all overdose, the possibility of multiple drug ingestion, including alcohol, should be considered.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Composition, and Packaging
Table 2: Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| oral | Extended-Release Powder for Oral Suspension 300 mg, 600 mg, 750 mg, and 900 mg/bottle (before reconstitution): 5 mg/mL after reconstitution | anhydrous citric acid, anhydrous trisodium citrate, banana flavour, corn starch, poloxamer 188, polyvinyl acetate, povidone, silicone dioxide, sodium benzoate, sodium polystyrene sulfonate, sucralose, sucrose, talc, triacetin, xanthan gum |
| oral | Extended-Release Chewable Tablets 20 mg, 30 mg, and 40 mg | aspartame, cherry flavor, citric acid, crospovidone, D&C red #30 (for 30 mg strength), D&C red #7 (for 40 mg strength), guar gum, magnesium stearate, mannitol, maltodextrin, microcrystalline cellulose, polyethylene glycol 3350, polysorbate 80, |
Description
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets utilize a drug delivery technology called LiquiXR. Each dose is made up of a combination of free drug, resin-bound uncoated immediate-release drug and resin-bound coated extended-release drug with variable thickness coating. This combination results in continuous release of methylphenidate in the gastrointestinal tract.
Quillivant ER Oral Suspension is supplied as powder that, after reconstitution with water, forms an extended-release oral suspension. Quillivant ER Oral Suspension contains approximately 20% immediate-release (present as particles of uncoated methylphenidate resin complex) and 80% extended-release methylphenidate (present as polymer coated methylphenidate resin complex). The product is supplied in a carton. Each carton also contains one bottle, one oral dosing dispenser, and one bottle adapter.
The product must be reconstituted only by the pharmacist and not by the patient or caregiver. After reconstitution, the product is a light beige to tan viscous suspension containing the equivalent of 5 mg per mL of methylphenidate hydrochloride.
Quillivant ER Chewable Tablets is supplied as a speckled capsule-shaped coated tablet containing 20 mg, 30 mg, or 40 mg of methylphenidate hydrochloride. The dosage strengths are expressed in terms of methylphenidate hydrochloride equivalents; however, only 15% of methylphenidate is present as methylphenidate hydrochloride salt. The remaining 85% is present as methylphenidate ionically-bound to the sulfonate groups of sodium polystyrene sulfonate particles (methylphenidate resin complex). Quillivant ER Chewable Tablets contains approximately 30% immediate-release (present as uncoated methylphenidate resin complex and free methylphenidate hydrochloride) and 70% extended-release methylphenidate (present as polymer coated methylphenidate resin complex). Quillivant ER Chewable Tablets 20 mg tablets are off-white and debossed with “NP 12” on one side and functionally scored on the other side. Quillivant ER Chewable Tablets 30 mg tablets are light pink and debossed with “NP 13” on one side and functionally scored on the other side. Quillivant ER Chewable Tablets 40 mg tablets are dark pink to peach and debossed with “NP 14” on one side and plain (not scored) on the other side. The tablets are supplied in bottles of 100.
7 Warnings and Precautions
Please see 3 Serious Warnings and Precautions Box at the beginning of Part I: Healthcare Professional Information.
General
- Drug treatment is not indicated in all cases of ADHD and should be considered only in light of the complete history and evaluation. The decision to prescribe Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should depend on the healthcare professional’s assessment of the chronicity and severity of the patient’s symptoms. Treatment should not depend solely on the presence of one or more abnormal behavioural characteristics. Where these symptoms are associated with acute stress reactions, treatment with methylphenidate is usually not indicated.
| polyvinyl acetate, polyvinyl alcohol, povidone, silicon dioxide, sodium lauryl sulfate, sodium polystyrene sulfonate, talc, triacetin, xanthan gum |
- All drugs with sympathomimetic effects prescribed in the management of ADHD should be used with caution in patients who: a) are involved in strenuous exercise or activities, b) use other sympathomimetic ADHD drugs or c) have a family history of sudden/cardiac death. Prior to the initiation of treatment, a personal and family history (including assessment for a family history of sudden death or ventricular arrhythmia) and physical exam should be obtained to assess for the presence of cardiac disease. In patients with relevant risk factors and based on the clinician’s judgment, further cardiovascular evaluation may be considered (e.g., electrocardiogram and echocardiogram). Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during ADHD treatment should undergo a prompt cardiac evaluation.
- Phenylalanine can be harmful to patients with phenylketonuria (PKU). Quillivant ER Chewable Tablets contain phenylalanine, a component of aspartame. Each 20 mg, 30 mg, and 40 mg extended-release chewable tablet contains 3 mg, 4.5 mg, and 6 mg phenylalanine, respectively. Before prescribing Quillivant ER Chewable Tablets in patients with PKU, consider the combined daily amount of phenylalanine from all sources, including Quillivant ER Chewable Tablets.
Carcinogenesis and Genotoxicity
See 16 Non-Clinical Toxicology section.
Cardiovascular
Sudden Death and Pre-existing Structural Cardiac Abnormalities or Other Serious Heart Problems
Children and Adolescents:
Sudden death has been reported in association with stimulant drugs used for ADHD treatment at usual doses in children and adolescents with structural cardiac abnormalities or other serious cardiac problems. Although some serious heart problems alone carry an increased risk of sudden death, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets generally should not be used in children or adolescents with known serious structural cardiac abnormalities, cardiomyopathy, serious heart rhythm abnormalities, or other serious cardiac problems that may place them at increased vulnerability to the sympathomimetic effects of a stimulant drug (see 2 Contraindications).
Adults:
Sudden death, stroke, and myocardial infarction have been reported in adults taking stimulant drugs at usual doses for ADHD. Although the role of stimulants in these adult cases is also unknown, adults have a greater likelihood than children of having serious structural cardiac abnormalities, cardiomyopathy, serious heart rhythm abnormalities, coronary artery disease, or other serious cardiac problems. Adults with such abnormalities should also generally not be treated with stimulant drugs (see 2 Contraindications).
Pre-existing Cardiovascular and Cerebral Vascular Conditions:
Central Nervous System (CNS) stimulants should be used with caution in patients with a pre-existing cardiovascular or cerebrovascular condition, taking into account risk predictors for these conditions. Patients should be screened for pre-existing or underlying cardiovascular or cerebrovascular conditions before initiation of treatment with stimulants and monitored for new conditions of the heart or brain during the course of treatment.
Hypertension and Other Cardiovascular Conditions
Hypertension may occur during methylphenidate treatment in some patients. Caution is particularly indicated in treating patients whose underlying medical conditions might be compromised by increases in blood pressure or heart rate, e.g., those with pre-existing hypertension, heart failure, recent myocardial infarction or hyperthyroidism.
Blood pressure should be monitored at appropriate intervals in patients receiving stimulants, especially in patients with pre-existing conditions that may result in hypertension.
Sympathomimetic medications cause a modest mean increase in blood pressure (about 2 to 4 mmHg) and heart rate (about 3 to 6 bpm) but individuals may have larger increases. In the placebo-controlled study of Quillivant ER Oral Suspension there were increases of up to 3.5 mmHg in systolic blood pressure, 6.0 mmHg in diastolic blood pressure, and 9.3 bpm in heart rate. In the placebo-controlled study Quillivant ER Chewable Tablets there were increases up to 7.0 mmHg in systolic blood pressure, 5.4 mmHg in diastolic blood pressure, and 11.6 bpm in heart rate. While the mean changes alone would not be expected to have short-term consequences, all patients should be monitored for larger changes in heart rate and blood pressure (see 2 Contraindications and 9 Drug Interactions).
Misuse and Serious Cardiovascular Adverse Events:
The misuse of central nervous system stimulants may cause serious cardiovascular adverse events and sudden death.
Peripheral Vasculopathy, Including Raynaud’s Phenomenon:
Stimulants used to treat ADHD, including methylphenidate products, are associated with peripheral vasculopathy, including Raynaud’s phenomenon. Signs and symptoms are usually intermittent and mild; however, very rare sequelae include digital ulceration and/or soft tissue breakdown. Effects of peripheral vasculopathy, including Raynaud’s phenomenon, were observed in post-marketing reports at different times and at therapeutic doses in all age groups throughout the course of treatment. Signs and symptoms generally improve after reduction in dose or discontinuation of drug. Careful observation for digital changes is necessary during treatment with ADHD stimulants. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Dependence, Tolerance and/or Abuse Liability
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be given cautiously to patients, particularly to those with a history of drug dependence or alcoholism, because such patients may increase dosage on their own initiative.
Chronic abusive use can lead to marked tolerance and psychological dependence with varying degrees of abnormal behaviour. Frank psychotic episodes can occur, especially with parenteral abuse.
Careful supervision is required during withdrawal from abuse since severe depression may occur. Withdrawal following chronic therapeutic use may unmask symptoms of an underlying disorder that may require follow-up.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery. Stimulants may impair the ability of the patient to operate potentially hazardous machinery or vehicles. Patients should be cautioned accordingly until they are reasonably certain that Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets does not adversely affect their ability to engage in such activities.
Endocrine and Metabolism
Long-Term Suppression of Growth
Sufficient data on the safety of long-term use of methylphenidate in children and adolescents are not yet available. Although a causal relationship has not been established, suppression of growth (i.e., weight gain and/or height) has been reported with the long-term use of stimulants in children. Therefore, patients requiring long-term therapy should be carefully monitored. Patients who are not growing or gaining weight as expected should have their treatment interrupted.
While Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are not indicated in pediatric patients under six years of age, stimulants, including methylphenidate, may lead to a greater risk of weight loss and other adverse reactions than in older children taking the same dose of the same medication (see 7.1.3 Pediatrics).
Monitoring and Laboratory Tests
Periodic laboratory tests are advised during prolonged therapy. The tests should include, but not be limited to, haematological parameters, including complete blood count, differential and platelet counts, and liver enzymes.
Neurologic
Seizures
There is some clinical evidence that methylphenidate may lower the convulsive threshold in patients with prior history of seizures, in patients with prior EEG abnormalities in the absence of seizures and, very rarely, in patients with no prior EEG evidence or history of seizures. Clinical experience has shown that a small number of patients may experience an increase in seizure frequency when treated with methylphenidate. In the presence of seizures or suspected seizures, the drug should be discontinued.
Motor and Verbal Tics, and Worsening of Tourette Syndrome
CNS stimulants, including methylphenidate, have been associated with the onset or exacerbation of motor and verbal tics. Worsening of Tourette syndrome has also been reported with other CNS stimulants. It is recommended that the family history be assessed, and that the patient is clinically evaluated for tics or Tourette syndrome before initiating methylphenidate. Regular monitoring for the emergence or worsening of tics or Tourette syndrome during treatment with methylphenidate is recommended at every dose adjustment and every visit, and treatment discontinued if clinically appropriate.
Serotonin toxicity / Serotonin syndrome:
Serotonin toxicity, also known as serotonin syndrome, is a potentially life-threatening condition and has been reported with methylphenidate, including Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets, with concomitant use of serotonergic or dopaminergic drugs (see 9.4 Drug-Drug Interactions, Serotonergic Drugs). Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets and other serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions, Serotonergic Drugs). If serotonin toxicity is suspected, discontinuation of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets and other serotonergic agents should be considered and appropriate treatment instituted.
Ophthalmologic
Increased intraocular pressure and glaucoma
There have been reports of elevation of intraocular pressure (IOP) and glaucoma associated with methylphenidate treatment. Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets are contraindicated in patients with glaucoma (see 2 Contraindications).
Visual Disturbance:
Symptoms of visual disturbances have been encountered in rare cases. Difficulties with accommodation and blurring of vision have been reported (see 8 Adverse Reactions).
Psychiatric
Pre-Existing Psychosis
Administration of stimulants may exacerbate symptoms of behaviour disturbance and thought disorder in patients with a pre-existing psychotic disorder.
Screening Patients for Bipolar Disorder
Particular care should be taken in using stimulants to treat ADHD in patients with comorbid bipolar disorder because of concern for possible induction of a mixed or manic episode in such patients. Prior to initiating treatment with a stimulant, patients with comorbid depressive symptoms should be adequately screened to determine if they are at risk for bipolar disorder. Such screening should include a detailed psychiatric history, including a family history of suicide, bipolar disorder and depression.
Emergence of New Psychotic or Manic Symptoms
Treatment-emergent psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in children and adolescents without a prior history of psychotic illness or mania can be caused by stimulants at usual doses. If such symptoms occur, consideration should be given to a possible causal role of the stimulant, and discontinuation of treatment may be appropriate. In a pooled analysis of multiple short-term, placebo-controlled studies, such symptoms occurred in about 0.1% (4 patients with events out of 3482 patients exposed to methylphenidate or amphetamine for several weeks at usual doses) of stimulant-treated patients compared to 0 in placebo-treated patients.
Aggression, Anxiety and Agitation
Patients with an element of agitation may react adversely; discontinue therapy if necessary.
Aggressive behaviour, marked anxiety or agitation are often observed in patients with ADHD, and have been reported in clinical trials and the post-marketing experience of some medications indicated for the treatment of ADHD. Although there is no systematic evidence that stimulants cause aggressive behaviour or hostility, patients beginning treatment for ADHD should be monitored for the appearance of or worsening of aggressive behaviour, marked anxiety, or agitation.
Suicidal Behaviour and Ideation
There have been post-marketing reports of suicide-related events in patients treated with ADHD drugs, including cases of ideation, attempts, and very rarely, completed suicide. The mechanism of this risk is not known. ADHD and its related co-morbidities may be associated with increased risk of suicidal ideation and/or behaviour.
Therefore, it is recommended for patients treated with ADHD drugs that caregivers and healthcare professionals monitor for signs of suicide-related behaviour, including at dose initiation/ optimization and drug discontinuation. Patients should be encouraged to report any distressing thoughts or feelings at any time to their healthcare professional. Patients with emergent suicidal ideation and behaviour should be evaluated immediately. The healthcare professionals should initiate appropriate treatment of the underlying psychiatric condition and consider a possible change in the ADHD treatment regimen (see 8.5 Post-Market Adverse Reactions).
Depression:
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should not be used to treat severe exogenous or endogenous depression.
Reproductive Health
Function:
- Priapism:
Prolonged and painful erections requiring immediate medical attention (sometimes including surgical intervention), have been reported with methylphenidate products in both pediatric and adult patients (see 8.5 Post-Market Adverse Reactions). Priapism can develop after some time on methylphenidate, often subsequent to an increase in dose. Priapism has also appeared during a period of methylphenidate withdrawal (drug holidays or during discontinuation). Patients who develop abnormally sustained erections or frequent and painful erections should seek immediate medical attention.
7.1 Special Populations
7.1.1 Pregnancy
Methylphenidate hydrochloride has been shown to have teratogenic effects in rabbits when given in doses of 200 mg/kg/day, which is approximately 100 times and 40 times the maximum recommended human dose on a mg/kg and mg/m2 basis, respectively.
Studies to establish safe use of methylphenidate in pregnant women have not been conducted. Therefore, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should not be given to pregnant women unless the potential benefit outweighs the risk to the fetus.
Embryo/Fetal/Neonatal Adverse Reactions
CNS stimulant medications, such as Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets, can cause vasoconstriction and thereby decrease placental perfusion. Premature delivery and low birth weight infants have been reported in amphetamine-dependent mothers.
7.1.2 Breastfeeding
A study conducted in rats indicated that the distribution profiles of methylphenidate in milk and plasma are similar. Case reports showed that methylphenidate was distributed into breast milk reaching a milk-to-plasma ratio of approximately 2.7 (see 10.3 Pharmacokinetics, Special Populations and Conditions, Pregnancy and Breastfeeding). There is one case report of an infant who experienced an unspecified decrease in weight during the period of exposure but recovered and gained weight after the mother discontinued treatment with methylphenidate. A risk to the suckling child cannot be excluded. A decision should be made whether to abstain from breastfeeding or to abstain from Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets therapy, taking into account the benefit of breastfeeding to the child and the benefit of therapy to the woman.
Monitor breastfeeding infants for adverse reactions, such as agitation, insomnia, anorexia, and reduced weight gain.
7.1.3 Pediatrics
Pediatrics (<6 years of age): Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should not be used in children under six years. Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in pediatric patients (<6 years of age) has not been established; therefore, Health Canada has not authorized an indication for pediatric use. Particular caution is warranted in this population due to a greater risk of weight loss and other adverse reactions associated with higher plasma exposures relative to patients 6 years and older at the same dose (see 7 Warnings and Precautions, Endocrine and Metabolism).
Pediatrics (6 – 12 years of age): Long-term effects Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets have not been well established beyond 8 weeks and 7 weeks, respectively.
Adolescents (13 – 17 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in adolescent patients has not been established; therefore, Health Canada has not authorized an indication for adolescent use.
7.1.4 Geriatrics
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets have not been studied in patients over the age of 65 years; therefore, Health Canada has not authorized an indication for geriatric use (see 1.2 Geriatrics).
8 Adverse Reactions
8.1 Adverse Reaction Overview
In the Quillivant ER Oral Suspension controlled study in children with ADHD, there were 3 subjects that experienced severe treatment-emergent adverse events (affect lability, aggression and initial insomnia) and 2 subjects that had adverse events that led to discontinuation during the open-label dose optimization phase. The most common adverse event (≥5%) during the open-label phase was decreased appetite. During the double-blind phase, there were no severe treatment-emergent adverse events or adverse events that led to discontinuation. There were no serious adverse events in the study. The most common adverse event (≥5%) during the double-blind phase was affect lability.
In the Quillivant ER Chewable Tablets controlled study in children with ADHD, there were 2 subjects that had adverse events that led to discontinuation during the open-label phase. The most common adverse event (≥5%) during the open-label phase was decreased appetite. During the double-blind phase, there were no adverse events that led to discontinuation. There were no severe or serious adverse events in the study. The most common adverse event (≥5%) during the double-blind phase was upper respiratory tract infection, which was reported at a similar rate in the placebo group.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The clinical trial program for Quillivant ER Oral Suspension included a total of 114 subjects including 44 pediatric (aged 6-12 years) ADHD patients in an 8-week, placebo-controlled, phase 3 double-blind classroom study. The clinical trial program for Quillivant ER Chewable Tablets included a total of 149 subjects including 90 pediatric (aged 6-12 years) ADHD patients in a 7-week, placebo-controlled, phase 3 double-blind classroom study.
The information included in this section is based on data from these studies. Adverse reactions were assessed by collecting adverse events (AEs), results of physical examinations, vital signs, weights, laboratory analyses, and ECGs.
The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event (TEAE) of the type listed. An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Adverse events observed with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets treatment mainly reflect side effects commonly associated with methylphenidate use. Very common AEs reported by patients treated with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets were: headache, insomnia, decreased appetite and abdominal pain. Most of the events were mild or moderate in severity.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Serious Adverse Events and Adverse Events Leading to Discontinuation of Treatment:
Children (6 to 12 years of age)
Quillivant ER Oral Suspension
In a placebo-controlled trial in children, during the double-blind treatment period, there were no discontinuations due to AEs or serious adverse events (SAEs) reported. During the open-label period, 4.4% (2/45) of Quillivant ER Oral Suspension-treated patients discontinued treatment due to AEs; one subject (2.2%) with severe affect lability and one subject (2.2%) with severe aggression. There were no SAEs reported.
Quillivant ER Chewable Tablets
In a placebo-controlled trial in children, during the double-blind treatment period, there were no discontinuations due to AEs or serious adverse events (SAEs) reported. During the open-label period, 2.2% (2/90) of Quillivant ER Chewable Tablets- treated patients discontinued treatment due to AEs; one subject (1.1%) with moderate dysgeusia and one subject (1.1%) with decreased appetite. There were no SAEs reported.
There is limited experience with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in controlled trials. TEAEs reported in controlled trials in children with ADHD treated with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets with an incidence greater or equal to 1% are presented in the tables below.
Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets
Table 3: Quillivant ER Oral Suspension: Treatment-Emergent Adverse Events Reported by ≥1% of Children (6 to 12 years of age) with ADHD in a Laboratory Classroom Study with up to 6 weeks Open Label Titration followed by a 2 week Double Blind, Placebo-Controlled Crossover Treatment Phase*
| Preferred Term | Open Label Phase (up to 6 weeks) N = 45 N (%) | Double-Blind Crossover Phase (2 weeks) | |
|---|---|---|---|
| Preferred Term | Open Label Phase (up to 6 weeks) N = 45 N (%) | Double-Blind Crossover Phase (2 weeks) | |
Placebo N = 45 N (%) | Quillivant ER Oral Suspension N = 45 N (%) | ||
Placebo N = 45 N (%) | Quillivant ER Oral Suspension N = 45 N (%) | ||
| Cardiac disorders | |||
| Palpitations | 1 (2.2) | 0 (0.0) | 0 (0.0) |
| Ear and labyrinth disorders | |||
| Motion sickness | 1 (2.2) | 0 (0.0) | 1 (2.2) |
| Eye disorders | |||
Vision blurred Eye pain | 1 (2.2) 0 (0.0) | 0 (0.0) 0 (0.0) | 0 (0.0) 1 (2.2) |
| Gastrointestinal disorders | |||
Abdominal pain upper Diarrhoea Nausea Vomiting Dry Mouth | 18 (40.0 2 (4.4) 2 (4.4) 2 (4.4) 1 (2.2) | 1 (2.2) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) | 1 (2.2) 0 (0.0) 0 (0.0) 1 (2.2) 0 (0.0) |
| General disorders and administration site conditions | |||
| Irritability | 6 (13.3) | 0 (0.0) | 0 (0.0) |
| Fatigue | 4 (8.9) | 0 (0.0) | 0 (0.0) |
| Metabolism and nutrition disorders | |||
| Decreased appetite | 25 (55.6) | 0 (0.0) | 1 (2.2) |
| Nervous system disorders | |||
Headache Dizziness Dizziness postural Lethargy Mental impairment Oromandibular dystonia | 7 (15.6) 3 (6.7) 1 (2.2) 1 (2.2) 1 (2.2) 1 (2.2) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) |
| Psychiatric disorders | |||
Affect lability Aggression Initial insomnia Insomnia Logorrhoea Aggression Change in sustained attention Nail picking Attention deficit/hyperactivity disorder Bruxism Depressed mood Social avoidant behaviour Stereotypy Tic | 12 (26.7) 0 (0.0) 9 (20.0) 8 (17.8) 4 (8.9) 3 (6.7) 2 (4.4) 2 (4.4) 1 (2.2) 1 (2.2) 1 (2.2) 1 (2.2) 0 (0.0) 0 (0.0) | 1 (1.2) 1 (2.2) 0 (0.0) 0 (0.0) 0 (0.0) 1 (1.2)) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 1 (2.2) 0 (0.0) | 4 (8.9) 0 (0.0) 1 (2.2) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 1 (2.2) |
| Respiratory, thoracic and mediastinal disorders | |||
| Oropharyngeal pain | 1 (2.2) | 0 (0.0) | 0 (0.0) |
| Skin and subcutaneous tissue disorders | |||
| Pruritus | 1 (2.2) | 0 (0.0) | 0 (0.0) |
| Vascular disorders | |||
| Flushing | 2 (4.4) | 0 (0.0) | 0 (0.0) |
* Study Duration: up to 8 weeks. Treatment period, including 4-6 weeks open-label dose titration (initial dose 20 mg titrated weekly in 10 or 20 mg increments until an optimal dose or the maximum dose of 60 mg/day was reached) followed by 2 weeks of stable dosing with Quillivant ER Oral Suspension or placebo administered in a randomized crossover fashion such that each patient received Quillivant ER Oral Suspension during one week and placebo during the other week.
Table 4: Quillivant ER Chewable Tablets: Treatment-Emergent Adverse Events Reported by ≥1% of Children (6 to 12 years of age) with ADHD in a Laboratory Classroom Study with up to 6 weeks Open Label Titration followed by a 1 week Double Blind, Placebo-Controlled Treatment Phase*
| Preferred Term | Open Label Phase (up to 6 weeks) N = 90 N (%) | Double-Blind Phase (1 week) | |
|---|---|---|---|
| Preferred Term | Open Label Phase (up to 6 weeks) N = 90 N (%) | Double-Blind Phase (1 week) | |
Placebo N = 44 N (%) | Quillivant ER Chewable Tablets N = 42 N (%) | ||
Placebo N = 44 N (%) | Quillivant ER Chewable Tablets N = 42 N (%) | ||
| Cardiac disorders | |||
| Tachycardia | 2 (2.2) | 0 (0.0) | 0 (0.0) |
| Ear and labyrinth disorders | |||
| Tinnitus | 2 (2.2) | 0 (0.0) | 0 (0.0) |
| Eye disorders | |||
Dry eye Excessive eye blinking | 1 (1.1) 1 (1.1) | 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) |
| Gastrointestinal disorders | |||
Abdominal pain upper Dry mouth Nausea Abdominal pain Vomiting Diarrhoea Dyspepsia Flatulence | 10 (11.1) 3 (3.3) 3 (3.3) 2 (2.2) 2 (2.2) 1 (1.1) 1 (1.1) 1 (1.1) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) 1 (2.4) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) |
| General disorders and administration site conditions | |||
Irritability Fatigue Feeling jittery | 11 (12.2) 2 (2.2) 2 (2.2) | 0 (0.0) 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) 0 (0.0) |
| Investigations | |||
Blood pressure systolic increased Weight decreased | 1 (1.1) 0 (0.0) | 0 (0.0) 0 (0.0) | 0 (0.0) 1 (2.4) |
| Metabolism and nutrition disorders | |||
| Decreased appetite | 33 (36.7) | 0 (0.0) | 1 (2.4) |
| Nervous system disorders | |||
Dysgeusia Headache Lethargy Dizziness Psychomotor hyperactivity Somnolence | 8 (8.9) 3 (3.3) 2 (2.2) 1 (1.1) 1 (1.1) 1 (1.1) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) |
| Psychiatric disorders | |||
Mood swings Insomnia | 12 (13.3) 10 (11.1) | 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) |
Initial insomnia Tic Middle insomnia Anger Change in sustained attention Onychophagia | 4 (4.4) 3 (3.3) 2 (2.2) 1 (1.1) 1 (1.1) 1 (1.1) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) | 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) 0 (0.0) |
| Renal and urinary disorders | |||
| Enuresis | 0 (0.0) | 1 (2.3) | 0 (0.0) |
| Respiratory, thoracic and mediastinal disorders | |||
| Epistaxis | 1 (1.1) | 0 (0.0) | 0 (0.0) |
| Skin and subcutaneous tissue disorders | |||
| Night sweats | 1 (1.1) | 0 (0.0) | 0 (0.0) |
* Study Duration: up to 7 weeks. Treatment period, including 6 weeks open-label dose titration (initial dose 20 mg titrated weekly in 10 or 20 mg increments until an optimal dose or the maximum dose of 60 mg/day was reached) followed by 1 week of stable dosing with Quillivant ER Chewable Tablets or placebo administered in a double-blind fashion such that each patient received either Quillivant ER Chewable Tablets or placebo for one week.
Additional Treatment-Emergent Adverse Events Reported During Clinical Trials with Other Methylphenidate Products
Commonly reported (≥2% of the methylphenidate group and at least twice the rate of the placebo group) adverse reactions from placebo-controlled trials of methylphenidate products include: appetite decreased, dyspepsia, anxiety, nervousness, restlessness, affect lability, agitation, irritability, vertigo, tremor, blurred vision, blood pressure increased, heart rate increased, tachycardia, palpitations, and hyperhidrosis.
8.5 Post-Market Adverse Reactions
- Suicidal Behaviour and Ideation
There have been post-marketing reports of suicide-related events, including completed suicide, suicide attempt, and suicidal ideation in patients treated with ADHD drugs. In some of these reports, comorbid conditions may have contributed to the event (see 7 Warnings and Precautions, Suicidal Behaviour and Ideation).
Adverse Events Reported with Methylphenidate Hydrochloride Products
The following adverse reactions have been identified during post approval use of methylphenidate products. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure. These adverse reactions are as follows:
Blood and Lymphatic System Disorders: Aplastic anemia, Pancytopenia, Thrombocytopenia, Thrombocytopenic purpura
Cardiac Disorders: Angina pectoris, Arrhythmia, Bradycardia, Extrasystole, Myocardial infarction, Supraventricular tachycardia, Ventricular extrasystole
Eye Disorders: Diplopia, Mydriasis, Visual impairment
Gastrointestinal Disorders: Constipation, Diarrhea, Pancreatitis
General Disorders and Administration Site Conditions: Chest pain, Chest discomfort, Hyperpyrexia
Hepatobiliary Disorders: Acute hepatic failure, Hepatocellular injury, Severe hepatocellular injury
Immune System Disorders: Hypersensitivity reactions such as Angioedema, Anaphylactic reactions, Auricular swelling, Bullous conditions, Exfoliative conditions, Urticarias, Pruritus NEC, Rashes, Eruptions, and Exanthemas NEC
Investigations: Alkaline phosphatase increased, Bilirubin increased, Hepatic enzyme increased, Platelet count decreased, White blood cell count abnormal
Musculoskeletal, Connective Tissue and Bone Disorders: Arthralgia, Myalgia, Muscle twitching, Rhabdomyolysis, Trismus
Nervous System Disorders: Cerebrovascular accident, Cerebrovascular disorder (including Cerebral vasculitis, Cerebral hemorrhage, Cerebral arteritis, Cerebral vascular occlusion), Convulsion, Dyskinesia, Grand mal convulsion, Serotonin syndrome in combination with serotonergic drugs
Psychiatric Disorders: Disorientation, Hallucination, Hallucination auditory, Hallucination visual, Libido changes, Mania, Complete Suicide, Suicide ideation, Suicide attempt, Obsessive-compulsive disorder, Psychotic disorder, Logorrhea, Libido disorder
Reproductive System and Breast Disorders: Gynecomastia, Priapism
Skin and Subcutaneous Tissue Disorders: Alopecia, Dermatitis exfoliative, Erythema
Vascular Disorders: Raynaud's phenomenon
Nervousness and insomnia are the most common adverse reactions reported with other methylphenidate products. Other reactions include hypersensitivity (including skin rash, urticaria, fever, arthralgia, exfoliative dermatitis, erythema multiforme with histopathological findings of necrotizing vasculitis, and thrombocytopenic purpura); anorexia; nausea; dizziness; headache; dyskinesia; drowsiness; blood pressure and pulse changes, both up and down; tachycardia; angina; abdominal pain; and weight loss during prolonged therapy. There have been rare reports of Tourette syndrome. Toxic psychosis has been reported. Although a definite causal relationship has not been established, the following have been reported in patients taking this drug: instances of abnormal liver function, e.g., hepatic coma; isolated cases of cerebral arteritis and/or occlusion; leukopenia and/or anemia; transient depressed mood; and a few instances of scalp hair loss. There have been reports of serotonin syndrome following coadministration of methylphenidate with serotonergic drugs. Very rare reports of neuroleptic malignant syndrome (NMS) have been received, and in most of these, patients were concurrently receiving therapies associated with NMS. In a single report, a ten-year-old boy who had been taking methylphenidate for approximately 18 months experienced an NMS-like event within 45 minutes of ingesting his first dose of venlafaxine. It is uncertain whether this case represented a drug-drug interaction, a response to either drug alone, or some other cause.
Although a definite causal relationship has not been established, the following have been reported in patients taking other methylphenidate products: instances of abnormal liver function, (e.g., hepatic coma); isolated cases of cerebral arteritis and/or occlusion; leukopenia and/or anemia; transient depressed mood; and a few instances of scalp hair loss. Very rare reports of Stevens-Johnson syndrome and neuroleptic malignant syndrome (NMS) have been received. In most of the NMS cases, patients were concurrently receiving therapies associated with NMS. In a single report, a ten-year-old boy who had been taking methylphenidate for approximately 18 months experienced an NMS-like event within 45 minutes of ingesting his first dose of venlafaxine. It is uncertain whether this case represented a drug-drug interaction, a response to either drug alone, or some other cause.
Priapism and Raynaud's phenomenon have also been reported with methylphenidate products.
9 Drug Interactions
9.1 Serious Drug Interactions
- Co-Administration of Monoamine Oxidase Inhibitors (MAOIs); see 2 Contraindications and 9.1 Drug-Drug Interactions, Monoamine Oxidase Inhibitors (MAOIs).
- Co-Administration of Clonidine; see 9.1 Drug-Drug Interactions, Clonidine.
9.2 Drug Interactions Overview
Because of possible increases in blood pressure and heart rate, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be used cautiously with drugs with similar pharmacological actions.
Patients should be advised not to consume alcohol while taking Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets.
Downward dose adjustment of anticoagulants, anticonvulsants and some antidepressants may be required when given concomitantly with methylphenidate.
Do not administer Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets concomitantly with monoamine oxidase inhibitors (MAOIs) or within 14 days after discontinuing MAOI treatment.
Serious adverse events including sudden death have been reported in concomitant use with clonidine.
9.3 Drug-Behaviour Interactions
Alcohol
The concomitant use of alcohol should be avoided (see 7 Warnings and Precautions, Dependence, Tolerance and/ or Abuse Liability).
Alcohol may exacerbate the CNS-related adverse effects of psychoactive drugs. Therefore, patients undergoing Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets therapy should be advised to avoid alcohol during treatment.
An in vitro study was conducted to explore the effect of alcohol on the release characteristics of methylphenidate from Quillivant ER Oral Suspension. At alcohol concentrations of 5% and 10%, there was no effect of alcohol on the release characteristics of methylphenidate. At 20% alcohol concentration, there was on average a 20% increase in drug exposure.
At 40% alcohol concentration, there was about 90% release methylphenidate from Quillivant ER Chewable Tablets 40 mg tablet within half an hour. The results with the 40 mg chewable tablet strength are considered representative of the other available tablet strengths.
Caffeine
Caffeine is a stimulant and may increase the risk of clinically significant blood pressure elevations when used in combination with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets. Advise patients to limit caffeine consumption within 24 hours prior to and following Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets administration (see 7 Warnings and Precautions, General and 7 Warnings and Precautions, Cardiovascular).
9.4 Drug-Drug Interactions
Vasopressor Agents
Because of possible increases in blood pressure, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets should be used cautiously with vasopressor agents (see 7 Warnings and Precautions, Cardiovascular, Hypertension and Other Cardiovascular Conditions).
Inhibition of Drug Metabolism by Methylphenidate
Human pharmacologic studies have shown that methylphenidate may inhibit the metabolism of coumarin anticoagulants (e.g., warfarin), anticonvulsants (e.g., phenobarbital, phenytoin, primidone) and some antidepressants (e.g., tricyclics, SSRIs). Downward dose adjustment of these drugs may be required when given concomitantly with methylphenidate. It may be necessary to adjust the dosage and monitor plasma drug concentrations (or, in the case of coumarin, coagulation times) when initiating or discontinuing concomitant methylphenidate.
Monoamine Oxidase Inhibitors (MAOIs)
Methylphenidate is contraindicated during treatment with MAOIs and also within a minimum of 14 days following discontinuation of a MAOI (hypertensive crises may result). The same precautions apply to Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets (see 2 Contraindications).
Clonidine
Serious adverse events including sudden death have been reported in concomitant use with clonidine. In these cases, no causality for the combination could be established because of insufficient data.
Anti-Hypertensive Drugs
Methylphenidate products may decrease the effectiveness of drugs used to treat hypertension (see 7 Warnings and Precautions, Cardiovascular, Hypertensions and Other Cardiovascular Conditions).
Antipsychotics
Because a predominant action of methylphenidate is to increase extracellular dopamine levels, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets may be associated with pharmacodynamic interactions when co-administered with some antipsychotics. Caution is warranted in patients receiving both Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets and an antipsychotic, as extrapyramidal symptoms could emerge when these drugs are administered concomitantly or when adjusting the dosage of one or both drugs.
Serotonergic Drugs
There have been reports of serotonin syndrome with methylphenidate, including Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets with concomitant use of serotonergic drugs. If concomitant treatment with Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets and other serotonergic agents is clinically warranted, careful observation of the patient is advised (see 7 Warnings and Precautions, Neurologic, Serotonin toxicity/ Serotonin syndrome). If serotonin toxicity is suspected, Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets (and serotonergic drugs) must be immediately discontinued and appropriate treatment instituted.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Methylphenidate HCl is a central nervous system (CNS) stimulant. The pharmacological properties of methylphenidate are similar to those of the amphetamines. However, in contrast to amphetamines, methylphenidate has more prominent effects on mental than motor activities. The mode of action of stimulants in ADHD is not completely understood, but they are thought to act primarily through indirect mechanisms, such as release of dopamine and norepinephrine from neuronal pools, and inhibition of neurotransmitter reuptake. Methylphenidate increases extracellular concentrations of dopamine and norepinephrine by inhibiting their neuronal reuptake, and is also an MAO. The behavioural and cognitive symptoms in ADHD and their response to stimulants are considered to reflect activity of dopaminergic and noradrenergic systems. Dopamine transporter binding sites are increased in the brains of ADHD patients and there is evidence for a genetic basis for this finding. Methylphenidate has been shown to both increase extracellular dopamine in the human brain and to reduce the number of dopamine transporter binding sites in patients with ADHD.
10.2 Pharmacodynamics
Methylphenidate exists as erythro and threo isomers but only the threo isomer possesses motor stimulant effects. Since both isomers inhibit monoamine oxidase, this suggests that this activity is not a primary mechanism of action of the dl-threo isomer when used clinically in ADHD.
Methylphenidate is a racemic mixture comprised of the d- and l-threo isomers. The d-isomer is more pharmacologically active than the l-isomer. dl-threo methylphenidate displays enantioselective pharmacokinetics. After administration of dl methylphenidate, plasma concentrations of d-methylphenidate are greater than those of l methylphenidate, due to preferential pre-systemic metabolism of the l-enantiomer to l-ritalinic acid. In addition, presence of the d-enantiomer inhibits the conversion of the l-enantiomer to ritalinic acid. The mode of therapeutic action in ADHD is not known. Methylphenidate blocks the reuptake of norepinephrine and dopamine into the presynaptic neuron and increases the release of these monoamines into the extraneuronal space.
Quillivant ER has a tablet and oral suspension formulation that uses a drug delivery technology called LiquiXR made up of resin-bound, uncoated immediate release drug and extended-release drug with variable coating. The combination of free drug, resin-bound uncoated drug and resin-bound coated drug with variable thickness coating results in continuous release of methylphenidate.
10.3 Pharmacokinetics
The single dose pharmacokinetics of d-MPH under fed conditions are summarized below from studies in children and adolescents with ADHD and healthy adults following an oral dose of 60 mg Quillivant ER.
Table 5: Summary of d-methylphenidate pharmacokinetic parameters after 60 mg Quillivant ER Oral Suspension
| Cmax | Tmax | t½ (h) | AUC0-∞ | CL | |||||||||
Children (n = 3) | 34.4 ± 14.0 | 4.05 (3.98 - 6.0) | 5.2 ± 0.1 | 378 ± 175 | 4.27 ± 0.70 | ||||||||
| Adolescents (n = 4) | 21.1 ± 5.9 | 2.0 (1.98 - 4.0) | 5.0 ± 0.2 | 178 ± 54.2 | 5.06 ± 1.42 | ||||||||
Adults (n = 27) | 17.0 ± 7.7 | 4.0 (1.3 - 7.3) | 5.2 ± 1.0 | 163.2 ± 80.3 | 5.66 ± 2.15 | ||||||||
* Breakfast was given 30 min prior to drug administration † total MPH measured in children (9-12 years old) and adolescents (13-15 years old), l-MPH <2% of d-MPH in circulation ‡ data presented as median (range) | |||||||||||||
Absorption: Following a single, 60 mg oral dose of Quillivant ER Oral Suspension in 28 healthy adult subjects in a crossover study under fasting conditions, d-methylphenidate (d-MPH) mean (± SD) peak plasma concentrations of 13.6 (± 5.8) ng/mL occurred at a median time of 5.0 hours after dosing (Figure 2). The relative bioavailability of Quillivant ER Oral Suspension compared to Methylphenidate IR oral solution (2x30 mg, q6h) is 95%.
Figure 2: Mean d-Methylphenidate Plasma Concentration-Time Profiles
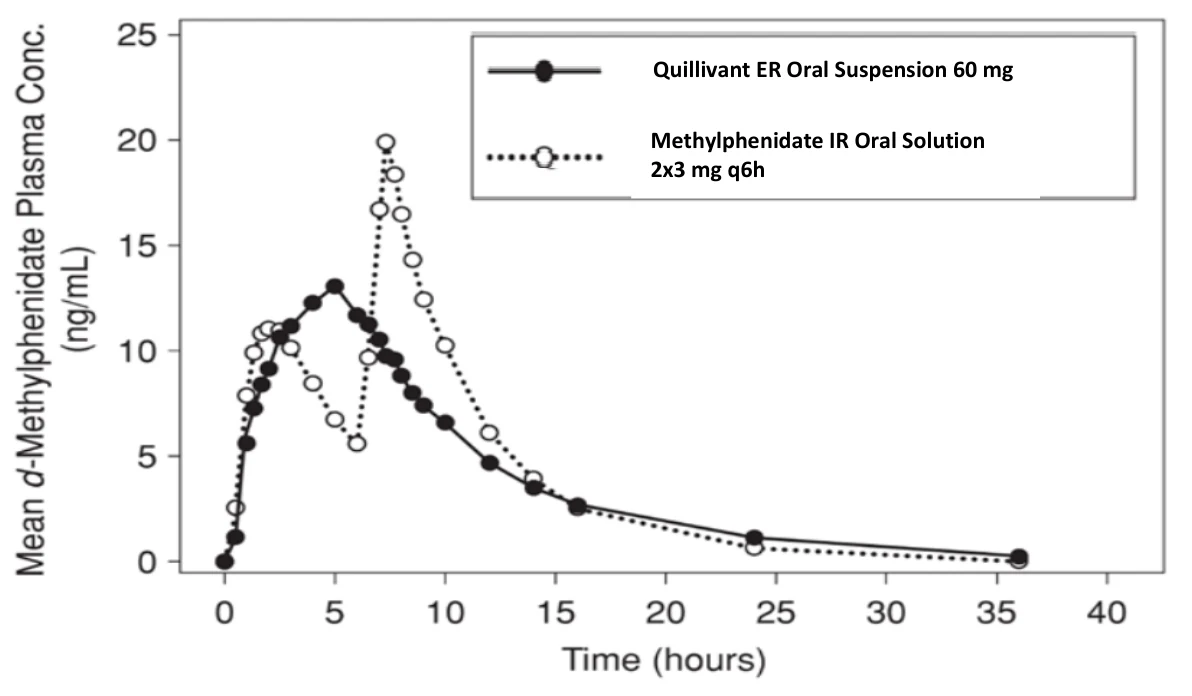
In a study in adult volunteers to investigate the effects of a high-fat meal on the bioavailability of Quillivant ER Oral Suspension at a dose of 60 mg, the presence of food reduced the time to peak concentration by approximately 1 hour (fed: 4 hours vs. fasted: 5 hours). Overall, a high-fat meal increased the average Cmax of Quillivant ER Oral Suspension by about 28% and the AUC by about 19%. These changes are not considered clinically significant.
Following a single oral dose of 40 mg Quillivant ER Chewable Tablets under fasting conditions, plasma methylphenidate reached maximal concentration (Cmax) at a median time of 5 hours after dosing. Compared to an immediate-release formulation of methylphenidate chewable tablet (40 mg in 2 equal doses of 20 mg, 6 hours apart), methylphenidate mean peak concentration and exposure (AUC∞) was about 20% and 11% lower, respectively, after single dose administration of 40 mg Quillivant ER Chewable Tablets (Figure 3).
Quillivant ER Oral Suspension 60 mg
Methylphenidate IR Oral Solution
2x3 mg q6h
Figure 3: Mean Methylphenidate Plasma Concentration-Time Profiles After Administration of 40 mg Quillivant ER Chewable Tablets or Methylphenidate Immediate-Release Chewable Tablets (IRCT, 2 Equal Doses of 20 mg, 6 Hours Apart) Under Fasted Conditions in Healthy Volunteers
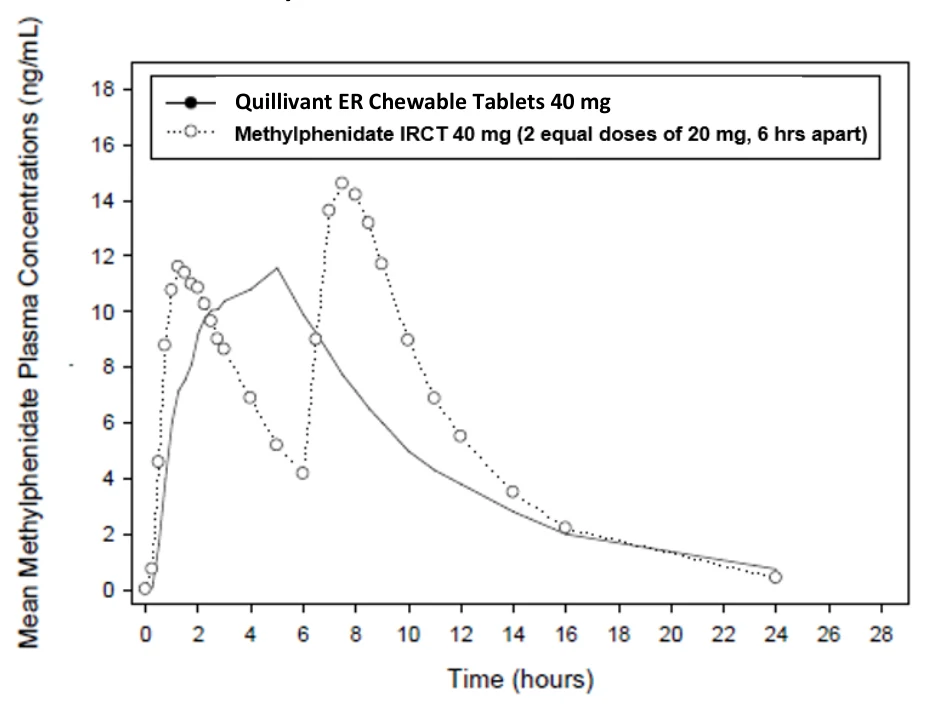
A high-fat meal had no effect on the time to peak concentration, and increased Cmax and systemic exposure (AUC∞) of methylphenidate by about 20% and 4%, respectively, after a single dose administration of 40 mg Quillivant ER Chewable Tablets.
Metabolism: In humans, methylphenidate is metabolized primarily via de-esterification to alpha-phenyl-piperidine acetic acid (PPAA). The metabolite has little or no pharmacologic activity.
Elimination: Plasma methylphenidate concentrations decline monophasically following oral administration. Following a single 60 mg oral dose of Quillivant ER Oral Suspension in 28 healthy adult subjects under fasting conditions, the mean plasma terminal elimination half-life of d-methylphenidate was 5.6 (± 0.8) hours. Following a single 40 mg dose of Quillivant ER Chewable Tablets the mean plasma terminal elimination half-life of methylphenidate was about 5.2 hours in healthy volunteers.
After oral dosing of radiolabeled methylphenidate in humans, about 90% of the radioactivity was recovered in urine. The main urinary metabolite was PPAA, accounting for approximately 80% of the dose.
Special populations and conditions
Pediatrics: The pharmacokinetics of methylphenidate after Quillivant ER Oral Suspension administration were studied in pediatric patients with ADHD between 9 and 15 years of age. After a single oral dose of 60 mg Quillivant ER Oral Suspension, plasma concentrations of methylphenidate in children (9 to 12 years old; n=3) were approximately twice the concentrations observed in adults. There are no specific pediatric pharmacokinetic studies for Quillivant ER Chewable Tablet. However, the pharmacokinetics of methylphenidate in pediatric patients 6 to 12 years old are not expected to be significantly different from adults following Quillivant ER Chewable Tablets administration.
Quillivant ER Chewable Tablets 40 mg
- Geriatrics: Specific studies of Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets in geriatric patients have not been conducted.
- Sex: There is insufficient experience with the use of Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets to detect gender variations in pharmacokinetics.
- Ethnic Origin: There is insufficient experience with the use of Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets to detect ethnic variations in pharmacokinetics.
- Pregnancy and Breastfeeding: Methylphenidate excretion into breast milk has been noted in two case reports, where the calculated relative infant dose was ≤0.2% of the weight adjusted maternal dose.
- Hepatic Insufficiency: There is no experience with the use of Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets in patients with hepatic insufficiency.
- Renal Insufficiency: There is no experience with the use of Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets in patients with renal insufficiency. After oral administration of radiolabeled methylphenidate in humans, methylphenidate was extensively metabolized and approximately 80% of the radioactivity was excreted in the urine in the form of PPAA. Since renal clearance is not an important route of methylphenidate clearance, renal insufficiency is expected to have little effect on the pharmacokinetics of Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets.
11 Storage, Stability, and Disposal
Store Quillivant ER Oral Suspension and Quillivant ER Chewable Tablets at 15°C to 30°C.
Dispense Quillivant ER Oral Suspension in its original container.
Store reconstituted Quillivant ER Oral Suspension at 15°C to 30°C. Quillivant ER Oral Suspension is stable for up to 4 months after reconstitution.
Dispose of remaining, unused, or expired Quillivant ER Oral Suspension or Quillivant ER Chewable Tablets at the pharmacy. Do not discard with household trash.
Part 2 : Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance: Methylphenidate hydrochloride
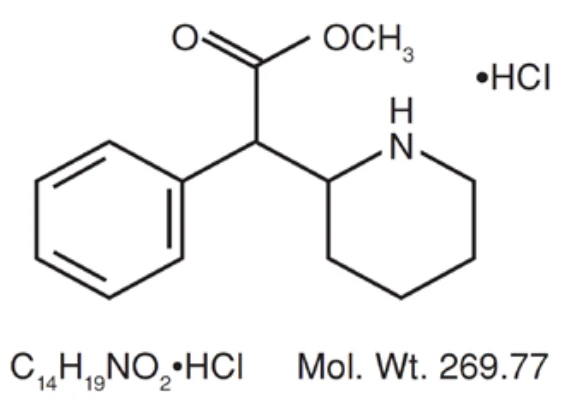
Chemical name: d,l(racemic) methyl α-phenyl-2-piperidineacetate hydrochloride
Molecular formula and molecular mass: C14H19NO2‧HCl, 269.77 g/mol
Structural formula:
Physicochemical properties: Methylphenidate hydrochloride USP is a white, odourless crystalline powder
pH: methylphenidate hydrochloride solutions are acidic to litmus
pKa: 8.9
Solubility: freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone
Melting Point: 224°C to 226°C
14 Clinical Trials
The efficacy of Quillivant ER Oral Suspension was evaluated in a laboratory classroom study conducted in 45 pediatric patients (ages 6 to 12 years) with ADHD. Patients in the trial met Diagnostic and Statistical Manual of Mental Diseases, 4th edition (DSM-IV) criteria for ADHD. The study began with an open-label dose optimization period (4 to 6 weeks) with an initial Quillivant ER Oral Suspension dose of 20 mg once daily in the morning. The dose could be titrated weekly in increments of 10 or 20 mg until a therapeutic dose or the maximum dose of 60 mg/day was reached. At the end of the dose optimization period, approximately 6.8% of subjects were receiving 20 mg/day; 68.2%, 30 mg/day - 40 mg/day; 25%, 50 mg/day - 60 mg/day. Subjects then entered a 2-week randomized, double-blind, crossover treatment with the individually optimized dose of Quillivant ER Oral Suspension or placebo. At the end of each week, school teachers and raters evaluated the attention and behavior of the subjects in a laboratory classroom using the Swanson, Kotkin, Agler, M-Flynn, and Pelham (SKAMP) rating scale. The
SKAMP rating scale is a 13-item teacher-rated scale that assesses manifestations of ADHD in a classroom setting and each item is rated on a 7-point impairment scale.
The efficacy of Quillivant ER Chewable Tablets was evaluated in a laboratory classroom study conducted in 90 pediatric subjects (ages 6 to 12 years) with ADHD. Patients in the trial met DSM-IV criteria for ADHD. The study began with a 6-week open-label dose optimization period with an initial Quillivant ER Chewable Tablets dose of 20 mg. Patients were instructed to chew each dose once daily in the morning. The dose could be titrated weekly in increments of 10 to 20 mg until a therapeutic dose or the maximum dose of 60 mg/day was reached. At the end of the dose optimization period, approximately 12.2% of subjects were receiving 20 mg/day; 43.3%, 30 mg/day - 40 mg/day; 44.5%, 50 mg/day - 60 mg/day.
14.1 Clinical Trials by Indication
Attention-Deficit Hyperactivity Disorder (ADHD)
Quillivant ER Oral Suspension
Table 6: Summary of patient demographics for the pivotal clinical trial of Quillivant ER Oral Suspension in ADHD (Study NWP06-ADD-100)*
| Study Design | Dosage, Duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|
| Phase 3, dose-optimized, randomized, double-blind, placebo-controlled, multicenter, laboratory classroom study | Open-Label Dose Optimization Period (6 weeks): initial methylphenidate dose for all subjects was 20 mg once daily in the morning with weekly titrations in increments of 10 or 20 mg until an optimal dose or maximum dose (60 mg/day) was reached. Double-blind treatment phase (2 weeks): Subjects were treated with active methylphenidate for one week, followed by placebo for one week (Sequence A) or vice versa (Sequence B). Subjects were treated with the optimal dose that was established in the open- label, optimization phase. | 44 | 8.8 years (6-12 years) | M-32 F-12 |
*Intent to treat population
The SKAMP rating scale is a 13-item teacher-rated scale that assesses manifestations of ADHD in a classroom setting and each item is rated on a 7-point impairment scale.
The primary efficacy endpoint was the SKAMP-Combined score at 4 hours post-dosing. The key secondary efficacy endpoints as determined by SKAMP-Combined scores at pre-dose and each post-dose (0.75, 2, 8, 10, and 12 hours) time point and each laboratory classroom day included onset and duration of clinical effect. The least-squares (LS) mean difference in SKAMP-Combined score at 4 hours post-dose was statistically significantly lower (i.e., more improved) with Quillivant ER Oral Suspension compared to placebo. Quillivant ER Oral Suspension was shown to have an onset of action within 0.75 hours (p<0.0001) and a duration of action of 12 hours (p = 0.0016) in children. Results from the two-week double-blind cross-over portion of the trial are summarized in Table 7 and depicted in Figure 4.
Table 7: Primary Efficacy Result (ITT Population)
Scale Time-point | Statistic | Treatment | Treatment Difference (Quillivant ER Oral Suspension – Placebo) (N = 44) | |
|---|---|---|---|---|
Placebo (N = 44) | Quillivant ER Oral Suspension (N = 44) | |||
SKAMP Combined Scale 4 Hours Post-Dose | N Mean (SD) Median Min, Max LS Mean (SE) 95% CI p-value Effect Size | 39 19.3 (8.38) 19.0 4, 40 19.58 (1.14) (17.31, 21.86) | 39 7.1 (5.64) 6.0 0, 30 7.12 (1.14) (4.85, 9.39) | 39 -12.2 (7.19) -10.0 -25, 0 -12.49 (1.13) (-14.75, -10.17) <0.0001 2.519 |
Abbreviations: CI=confidence interval
Figure 4: SKAMP-Combined Scores Over Time (LS Mean ± SE) by Treatment Arm in a 2-Sequence, Cross-over, Laboratory Study (ITT Population) of Quillivant ER Oral Suspension in Patients (6 to 12 years old) with ADHD (N=44)
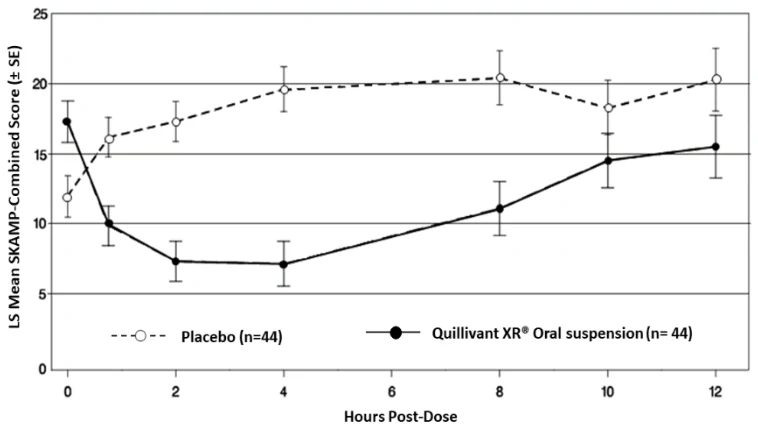
ITT: Intent-to-treat. LS means from post-dose time points were obtained from a repeated measures mixed model with terms for centre, hour, treatment and treatment-by-hour interaction. For the pre-dose time-point, arithmetic means and standard errors are displayed. Lower scores depict improvement.
Quillivant ER Chewable Tablets
Table 8: Summary of patient demographics for the pivotal clinical trial of Quillivant ER Chewable Tablets in ADHD (Study B7491005)*
| Study Design | Dosage, Duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|
| Phase 3, dose-optimized, randomized, double-blind, placebo-controlled, multicenter, laboratory classroom study | Open-Label Dose Optimization Period (6 weeks): Methylphenidate hydrochloride ERCT 20-60 mg/day taken orally once daily in the morning before 10:00 am. Starting dose of 20 mg/day could be titrated up or down based on clinical judgment at weekly intervals in 10-20 mg/day increments to achieve a stable dose of 20-60 mg/day. Double-blind treatment phase (1 week): Subjects were randomized to receive methylphenidate hydrochloride ERCT (at the optimized dose) or placebo taken orally once daily in the morning before 10:00 am at the optimal dose established in the Dose-Optimization Period. | 90 | 9.6 years (6-12 years) | M-53 F-32 |
*Intent to treat population
Eighty-six (86) of the 90 enrolled subjects then entered a 1-week randomized, double-blind, parallel group treatment period with the individually optimized dose of Quillivant ER Chewable Tablets or placebo. The intent-to-treat (ITT) population consisted of 85 randomized subjects who received at least 1 dose of double-blind study drug and had at least 1 post-Baseline assessment of the primary efficacy variable. At the end of the double-blind treatment period, the laboratory classroom raters and teachers evaluated the attention and behavior of the subjects, throughout the day using the SKAMP rating scale.
The SKAMP-Combined score, measured at 0.75, 2, 4, 8, 10, 12, and 13 hours post-dose during the laboratory classroom day at the end of the double-blind treatment period, was used to assess the primary and the key secondary efficacy parameters. The primary efficacy endpoint was the average of treatment effects across all the time points as specified above during the classroom day. The key secondary efficacy parameters were onset and duration of clinical effect.
The least-squares (LS) mean difference in the average of all post-dose SKAMP-Combined scores was statistically significantly lower (i.e., more improved) with Quillivant ER Chewable Tablets compared to placebo. Quillivant ER Chewable Tablets was shown to have an improvement over placebo as early as 45 minutes (with an onset of action up to 2 hours, p < 0.001) and a duration of action of 8 hours (p < 0.001) in children. Results from the two-week double-blind cross-over portion of the trial are summarized in Table 9. Efficacy results at each timepoint are summarized in Figure 5.
Table 9: Primary Efficacy Result (ITT Population)
| Study Number | Treatment Group | Primary Efficacy Measure: Average of Treatment Effect Across All TimePoints Based on SKAMP-Combined Score | |
|---|---|---|---|
Mean Pre-dose Score on Classroom Day (SD) | LS Mean (SE) for the Classroom Day | Placebo-subtracted Differencea (95% CI) | |
| Study 1 | |||
| Quillivant ER Chewable Tablets (N=42) | 17.5 (11.6) | 12.1 (1.4) | |
| -7.0 (-10.9, -3.1) | |||
| Placebo (N=43) | 13.8 (10.0) | 19.1 (1.4) | |
N: number of patients; SD: standard deviation; SE: standard error; LS Mean: least-squares mean; CI: confidence Interval.
aLeast-squares Mean Difference (drug minus placebo).
Figure 5: SKAMP-Combined Scores Over Time (LS Mean ± SE) by Treatment Group (ITT Population) in a Laboratory Classroom Study of Quillivant ER Chewable Tablets in Patients (6 to 12 years old) with ADHD (N=85)
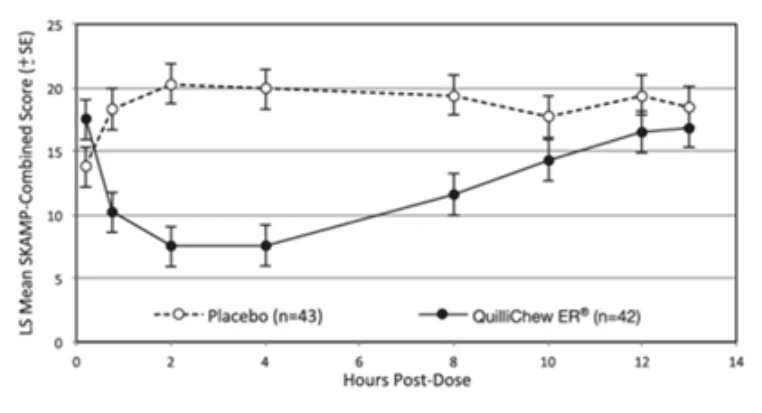
ITT: Intent-to-treat. LS means from post-dose time points were obtained from a repeated measures mixed model with terms for centre, hour, treatment and treatment-by-hour interaction. For the pre-dose time-point, arithmetic means and standard errors are displayed. Lower scores depict improvement.
16 Non-Clinical Toxicology
Genotoxicity: Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay or in the in vitro mouse lymphoma cell forward mutation assay. Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary (CHO) cells. Methylphenidate was negative in an in vivo mouse bone marrow micronucleus assay.
Carcinogenicity: In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate caused an increase in hepatocellular adenomas and, in males only, an increase in hepatoblastomas, at a daily dose of approximately 60 mg/kg/day. This dose is approximately 3.4 times the maximum recommended human dose (for a 30 kg child) on a mg/m2 basis. Hepatoblastoma is a relatively rare rodent malignant tumor type. There was no increase in total malignant hepatic tumors. The mouse strain used is sensitive to the development of hepatic tumors, and the significance of these results to humans is unknown.
Methylphenidate did not cause any increase in tumors in a lifetime carcinogenicity study carried out in
F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 5 times the maximum recommended human dose on a mg/m2 basis.
Reproductive and developmental toxicology: Methylphenidate did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week Continuous Breeding study. The study was conducted at doses of up to 160 mg/kg/day, approximately 8-fold the maximum recommended human dose on a mg/m2 basis.
No teratogenic effects were seen in rats when given at a dose of 75 mg/kg/day, which are 37.5 and 8.2 times the maximum recommended human dose on a mg/kg and mg/m2 basis, respectively. In another study, however, methylphenidate was shown to be teratogenic in rabbits when given at a dose of 200 mg/kg/day, which are approximately 100 times and 40 times higher than the maximum recommended human dose on a mg/kg and mg/m2 basis, respectively.
Juvenile toxicity: Rats treated with methylphenidate early in the postnatal period through sexual maturation demonstrated a decrease in spontaneous locomotor activity in adulthood. A deficit in acquisition of a specific learning task was observed in females only.
In the study conducted in young rats, methylphenidate was administered orally at doses of up to 100 mg/kg/day for 9 weeks, starting early in the postnatal period (postnatal day 7) and continuing through sexual maturity (postnatal week 10). When these animals were tested as adults (postnatal weeks 13-14), decreased spontaneous locomotor activity was observed in males and females previously treated with 50 mg/kg/day (approximately 4.4 times the maximum human recommended dose MHRD) on a mg/m2 basis) or greater, and a deficit in the acquisition of a specific learning task was observed in females exposed to the highest dose ( approximately 9 times the MHRD on a mg/m2 basis). The no effect level for juvenile neurobehavioral development in rats was 5 mg/kg/day (approximately half the MHRD on a mg/m2 basis). The clinical significance of the long-term behavioral effects observed in rats is unknown.