


Product Monograph - Amikin
INDICATIONS AND CLINICAL USE
AMIKIN is indicated in the short term treatment of serious infections due to susceptible strains of Pseudomonas species, Escherichia coli, Proteus species, Klebsiella - Enterobacter - Serratia species, Providencia species, Salmonella species, Citrobacter species and Staphylococcus aureus.
Clinical studies have shown AMIKIN to be effective in bacteremia, septicemia (including neo-natal sepsis), osteomyelitis, septic arthritis; respiratory tract, urinary tract, intra-abdominal (including peritonitis) infections and soft tissue abscesses.
Appropriate bacteriological studies should be performed in order to identify and determine the susceptibility of the causative organism. Relevant surgical procedures should be performed when indicated.
CONTRAINDICATIONS
AMIKIN is contraindicated in patients with known allergy to amikacin or any component of the formulation. A history of hypersensitivity or serious toxic reactions to aminoglycosides may contraindicate the use of any aminoglycoside because of the known cross sensitivities of patients to drugs in this class.
WARNINGS
Patients receiving AMIKIN should be under close observation and evaluation because of the potential ototoxicity and nephrotoxicity associated with its use. Safety for treatment periods which are longer than 14 days has not been established.
Neurotoxicity, manifested as vestibular and/or bilateral auditory ototoxicity, can occur in patients treated with aminoglycosides. The risk of aminoglycoside-induced ototoxicity is greater in patients with impaired renal function, and in those who receive high doses, or in those whose therapy is prolonged. High frequency deafness usually occurs first and can be detected only by audiometric testing. Vertigo may occur and may be evidence of vestibular injury. Other manifestations of neurotoxicity may include numbness, skin tingling, muscle twitching and convulsions. The risk of ototoxicity due to aminoglycosides increases with the degree of exposure to either persistently high peak or high trough serum concentrations. Patients developing cochlear or vestibular damage may not have symptoms during therapy to warn them of developing eighth nerve toxicity, and total or partial irreversible bilateral deafness or disabling vertigo may occur after the drug has been discontinued. Aminoglycoside-induced ototoxicity is usually irreversible.
Aminoglycosides are potentially nephrotoxic. The risk of nephrotoxicity is greater in patients with impaired renal function, and in those who receive high doses, or in those whose therapy is prolonged.
Renal and eighth-cranial nerve function should be closely monitored especially in patients with known or suspected renal impairment at the onset of therapy, and also in those whose renal function is initially normal but who develop signs of renal dysfunction during therapy. Serum concentrations of amikacin should be monitored when feasible to assure adequate levels and to avoid potentially toxic levels. Urine should be examined for decreased specific gravity, increased excretion of proteins, and the presence of cells or casts. Blood urea nitrogen, serum creatinine, or creatinine clearance should be measured periodically. Serial audiograms should be obtained where feasible in patients old enough to be tested, particularly high risk patients. Evidence of ototoxicity (dizziness, vertigo, tinnitus, roaring in the ears, and hearing loss) or nephrotoxicity requires discontinuation of the drug or dosage adjustment.
Concurrent and/or sequential systemic, oral, or topical use of other neurotoxic or nephrotoxic products, particularly bacitracin, cisplatin, amphotericin B, cephaloridine, paromomycin, viomycin, polymyxin B, colistin, vancomycin, or other aminoglycosides should be avoided. Other factors that may increase risk of toxicity are advanced age and dehydration.
The concurrent use of AMIKIN with potent diuretics (ethacrynic acid, or furosemide) should be avoided since diuretics by themselves may cause ototoxicity. In addition, when administered intravenously, diuretics may enhance aminoglycoside toxicity by altering antibiotic concentrations in serum and tissue.
Neuromuscular blockade and respiratory paralysis have been reported following parenteral injection, topical instillation (as in orthopedic and abdominal irrigation or in local treatment of empyema), and following oral use of aminoglycosides. The possibility of respiratory paralysis should be considered if aminoglycosides are administered by any route, especially in patients receiving anesthetics, neuromuscular blocking agents such as tubocurarine, succinylcholine, decamethonium, or in patients receiving massive transfusions of citrate-anticoagulated blood. If neuromuscular blockade occurs, calcium salts may reverse respiratory paralysis, but mechanical respiratory assistance may be necessary.
AMIKIN contains sodium bisulfite, a sulfite that may cause allergic-type reactions including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in certain susceptible people. The overall prevalence of sulfite sensitivity in the general population is uncommon and probably low. Sulfite sensitivity is seen more frequently in asthmatic than in nonasthmatic subjects.
If AMIKIN is used concurrently with other antibacterial agents to treat mixed or superinfections, it should not be physically mixed. Each agent should be administered separately in accordance with its recommended route of administration and dosage schedule.
PRECAUTIONS
Aminoglycosides are quickly and almost totally absorbed when they are applied topically, except to the urinary bladder, in association with surgical procedures. Irreversible deafness, renal failure and death due to neuromuscular blockade have been reported following irrigation of both small and large surgical fields with an aminoglycoside preparation.
The concurrent or serial use of other ototoxic or nephrotoxic agents should be avoided either systemically or topically because of the potential for additive effects. Increased nephrotoxicity has been reported following concomitant parenteral administration of aminoglycoside antibiotics and cephalosporins. Concomitant cephalosporin use may spuriously elevate creatinine serum level determinations.
Ototoxicity
A pre-treatment audiogram should be performed in patients with renal and pre-existing eighth nerve impairment and an audiogram should be repeated during therapy. When tinnitus or subjective hearing loss occurs in patients, the attending physician should strongly consider discontinuing treatment with AMIKIN. (See WARNINGS).
Nephrotoxicity
Patients should be well hydrated during treatment and renal function should be assessed by the usual methods prior to starting therapy and daily during the course of treatment. A reduction of dosage (see DOSAGE AND ADMINISTRATION) is required if evidence of renal dysfunction occurs such as presence of urinary casts, white or red cells, albuminuria, decreased creatinine clearance, decreased urine specific gravity, increased BUN, serum creatinine, or oliguria. If azotemia increases, or if a progressive decrease in urinary output occurs, treatment should be stopped.
Elderly patients may have reduced renal function which may not be evident in routine screening tests such as BUN or serum creatinine. A creatinine clearance determination may be more useful. Monitoring of renal function in elderly patients during treatment with aminoglycosides is particularly important.
Neurotoxicity
Neuromuscular blockade and muscular paralysis have been demonstrated in laboratory animals given high doses of amikacin. The possibility of neuromuscular blockade and respiratory paralysis should be considered when amikacin is administered concomitantly with anesthetic or neuromuscular blocking drugs. If blockade occurs, calcium salts may reverse this phenomenon.
Aminoglycosides should be used with caution in patients with muscular disorders such as myasthenia gravis or parkinsonism since these drugs may aggravate muscle weakness because of their potential curare-like effect on the neuromuscular junction.
Pregnancy
Aminoglycosides can cause fetal harm when administered to a pregnant woman. Aminoglycosides cross the placenta and there have been several reports of total irreversible, bilateral congenital deafness in children whose mothers received streptomycin during pregnancy. Although serious side effects to the fetus or newborns have not been reported in the treatment of pregnant women with other aminoglycosides, the potential for harm exists. Reproduction studies of amikacin have been performed in rats and mice and revealed no evidence of impaired fertility or harm to the fetus due to amikacin. There are no well controlled studies in pregnant women, but investigational experience does not include any positive evidence of adverse effects to the fetus. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
Nursing Mothers
It is not known whether this drug is excreted in human milk. As a general rule, nursing should not be undertaken while a patient is receiving any drug, since many drugs are excreted in human milk.
Pediatric Use
Aminoglycosides should be used with caution in premature and neonatal infants because of the renal immaturity of these patients and the resulting prolongation of serum half-life of these drugs.
Other
As with other antibiotics, the use of amikacin may result in overgrowth of nonsusceptible organisms. If this occurs, appropriate therapy should be instituted.
In vitro admixture of aminoglycosides with beta-lactam antibiotics (penicillins or cephalosporins) may result in significant mutual inactivation. A reduction in serum activity may also occur when an aminoglycoside or penicillin-type drug is administered in vivo by separate routes. Inactivation of the aminoglycoside is clinically significant only in patients with severely impaired renal function. Inactivation may continue in specimens of body fluids collected for assay, resulting in inaccurate aminoglycoside readings. Such specimens should be properly handled (assayed promptly, frozen, or treated with beta-lactamase).
ADVERSE REACTIONS
All aminoglycosides have the potential to induce ototoxicity, renal toxicity and neuromuscular blockade (see Warnings and Precautions). These toxicities occur more frequently in patients with renal impairment, in patients treated with other ototoxic or nephrotoxic drugs, and in patients treated for longer periods and/or with higher doses than recommended.
Nephrotoxicity - Renal failure, abnormal urinalysis, including albuminuria, presence of red and white cells and granular casts; azotemia, hemoglobinuria, oliguria, elevated BUN or serum creatinine levels or a decrease in creatinine clearance. In most cases, these changes have been reversible when the drug has been discontinued.
As would be expected with any aminoglycoside, reports of toxic nephropathy and acute renal failure have been received during postmarketing surveillance.
Neurotoxicity-Ototoxicity - Toxic effects on the eighth cranial nerve can result in hearing loss, loss of balance, or both. Amikacin primarily affects auditory function. Cochlear damage includes high frequency deafness and usually occurs before clinical hearing loss can be detected by audiometric testing. Tinnitus, vertigo, dizziness, nystagmus, fullness in ear, staggering, and partial (reversible to irreversible) deafness have been reported, usually associated with higher than recommended dosage. Rapid development of hearing loss may occur in patients with poor kidney function treated concurrently with AMIKIN and one of the rapidly acting diuretic agents given intravenously. These have included ethacrynic acid, furosemide and mannitol.
Neurotoxicity-Neuromuscular Blockage - Acute muscular paralysis and apnea can occur following treatment with aminoglycoside drugs.
Other - The following adverse reactions of the drug have also been observed: skin rash, drug fever, nausea and vomiting, headache, paresthesia, arthralgia, hypomagnesemia, tremor, eosinophilia, anemia, and hypotension. When administered intramuscularly, mild to severe pain at injection sites, as well as localized burning and erythema. Induration and sterile ulcers have been noted on rare occasions. Macular infarction sometimes leading to permanent loss of vision has been reported following intravitreous administration (injection into the eye) of amikacin. The following adverse effects have been observed although it is felt they are not drug-related: hematological changes including decrease in hematocrit and hemoglobin, thrombocytopenia, granulocytopenia/lymphocytosis; hepatic changes, including increased serum bilirubin, serum transaminases (SGOT, SGPT), hepatic enzymes, and alkaline phosphatase; pruritus, upper gastrointestinal bleeding, diarrhea, fatigue, weakness, focal premature nodal and ventricular contractions, vasoconstriction, seizures, Bell's palsy, phlebitis and thrombophlebitis.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
In the event of overdosage or toxic reactions, peritoneal dialysis or hemodialysis will aid in the removal of amikacin from the blood. Amikacin levels are also reduced during continuous arteriovenous hemofiltration. In the newborn infant, exchange transfusion may also be considered. These procedures are of particular importance in patients with impaired renal function.
DOSAGE AND ADMINISTRATION
A maximum total adult dose of 15 g during a course of treatment by all recommended routes of administration should not be exceeded. Treatment should not exceed 1.5 g per day and should not be administered for longer than 10 days. In the unusual circumstance, where treatment beyond 10 days or a dose larger than 1.5 g daily or 15 g total is considered, the use of AMIKIN should be re-evaluated. If administration of AMIKIN is prolonged, renal and auditory functions, and serum amikacin levels should be monitored daily.
Whenever possible, amikacin concentrations in serum should be measured to assure adequate, but not excessive levels. It is desirable to measure both peak and trough serum concentrations intermittently during therapy. Peak concentrations (30-90 minutes after injection) above 35 mcg/mL and trough concentrations (just prior to the next dose) above 10 mcg/mL should be avoided. Dosage should be adjusted as indicated.
At the recommended dosage level, uncomplicated infections due to amikacin-sensitive organisms should respond in 24 to 48 hours. If definite clinical response does not occur within 3 to 5 days, therapy should be stopped and the antibiotic susceptibility pattern of the invading organism should be rechecked. Failure of the infection to respond may be due to resistance of the organism or to the presence of septic foci requiring surgical drainage. Administration in Patients with Impaired Renal Function
In patients with impaired renal function, it is necessary to prolong the interval between doses.
One suggested method for estimating dosage in patients with known or suspected diminished renal function is to multiply the serum creatinine concentration level (mg/100 mL) by 9 and to use the resulting figure as the interval (in hours) between doses (see below); e.g.: if the creatinine concentration is 2.0 mg/100 mL, the recommended dose (7.5 mg/kg) should be administered every 18 hours. It should be emphasized that since renal function may alter appreciably during therapy, the serum creatinine should be checked frequently. Changes in the concentration would, of course, necessitate changes in the dosage frequency.
The dosage interval may be calculated by the following formula:
Serum creatinine (mg/100 mL) x 9 = Dosage interval (in hours).
If there is evidence of progressive renal dysfunction during therapy, discontinuation of the drug should be considered.
These dosage schedules must be used in conjunction with careful clinical and laboratory observations of the patient and should be modified as necessary, including modification when dialysis is being performed.
Infants and Neonates
In order to insure adequate therapeutic concentrations, which may be critical, while at the same time avoiding potentially toxic concentrations, serum concentrations should be monitored.
Dosage in Adults, Children and Neonates
The patient's pretreatment body weight should be obtained for calculation of correct dosage.
Intramuscular Route
The recommended daily dose for AMIKIN is 15 mg/kg to be administered at 7.5 mg/kg every 12 hours (500 mg twice a day).
Intravenous Administration
The recommended daily dose for AMIKIN is 15 mg/kg to be administered at 7.5 mg/kg every 12 hours (500 mg twice a day). The solution for intravenous use is prepared by adding the contents of 500 mg/2 mL vial to 250 mL of sterile diluent and is administered over a 30-60 minute period. Solutions for intravenous administration should be used within 12 hours after preparation.
AMIKIN has been found to be compatible with the following intravenous solutions:
Utility Time (Hours) for Amikacin in Intravenous Solution (25°C)
| I.V. Solution | 0.25 mg AMIKIN/mL HRS. | 5.0 mg AMIKIN/mL HRS. |
| Normal Saline | 12 | 12 |
| .25% Sodium Chloride in Water | 12 | 12 |
| Sterile Water for Inj., U.S.P. | 12 | 12 |
| 5% Dextrose U.S.P. | 12 | 12 |
| 2.5% Dextrose & 0.9% Sodium Cl | 12 | 12 |
| 5% Dextrose & 0.33% Sodium Cl | 12 | 12 |
| 5% Dextrose in Ringer’s Inj. | 12 | 12 |
| 10% Invert Sugar in 0.9% Sodium Cl | 12 | 12 |
| Lactated Ringer’s Inj. U.S.P. | 12 | 12 |
| Ringer’s Inj. U.S.P. | 12 | 12 |
| Ionosol D-C M* | 12 | 12 |
* Electrolyte Solution containing the following mEq/liter: sodium 138, Potassium 12,
Magnesium 3, Chloride 108, Calcium 5, Lactate 50.
If AMIKIN is used concurrently with other antibacterial agents to treat mixed or superinfections, it should not be physically mixed. Each agent should be administered separately in accordance with its recommended route of administration and dosage schedule.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever the solution and container permit.
Because of the potential toxicity of aminoglycosides, "fixed dosage" recommendations which are not based upon body weight are not advised. Rather, it is essential to calculate the dosage to fit the needs of each patient.
AVAILABILITY AND DOSAGE FORMS
AMIKIN is supplied as an aqueous solution of amikacin sulfate in single dose vials of:
500 mg in 2 mL volume, each mL contains 250 mg of amikacin activity, buffered with 2.5% sodium citrate and preserved with 0.66% sodium bisulfite.
The solution has a pH of 4.5.
PHARMACEUTICAL INFORMATION
Amikacin (contained in the solution as a 1:2 sulfate)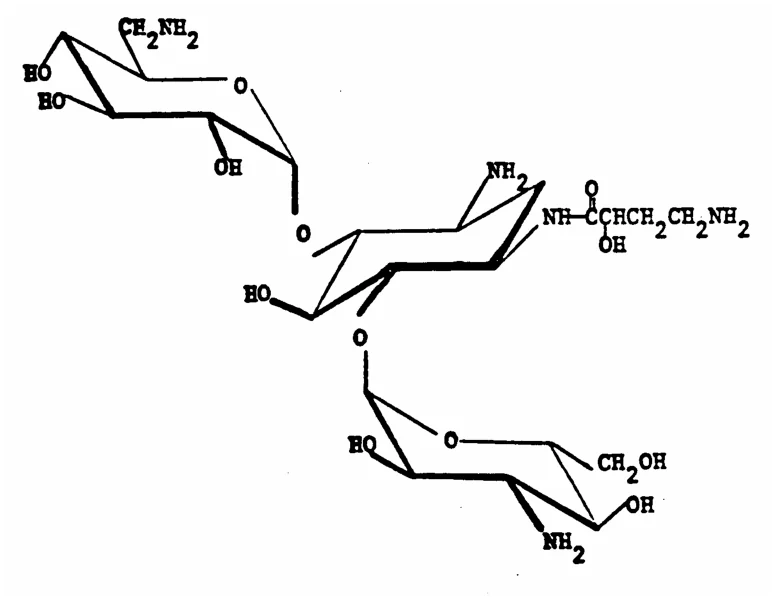
Molecular Formula: C22H43N5O13
Molecular Weight: 585.63
Chemical Name: 1-N[L(-)-4-amino-2-hydroxybutyryl] Kanamycin A.
Description:
Amikacin is a white to off-white powder. It is freely soluble in water as a sulfate.The base has the following characteristics: m.p. 203-204°C; specific rotation +99° (in water, 2%).
AMIKIN is supplied as a colourless solution which requires no refrigeration. At times the solution becomes a pale yellow; however, this does not indicate a loss of potency. Dark coloured solutions should be discarded.
PHARMACOLOGY
Amikacin is readily available and rapidly absorbed via the intravenous and intramuscular routes of administration. Figure I indicates the plasma levels attained after both forms of administration. The mean serum half-life is 2.2 hours with a mean renal clearance rate of 1.24 mL/kg/minute. No accumulation is associated with dosing at 12 hour intervals in individuals with a normal renal function.
In 36 neonates, after intramuscular or intravenous administration of 7.5 mg/kg every 12 hours, the mean serum half-life is 5.4 ± 2.0 hours and the mean peak serum level is 17.7 ± 5.4 :g/mL. No accumulation has been observed for a dosing period of 10 to 14 days. After an intramuscular dose of 7.5 mg/kg to 8 neonates, the mean peak serum level was reached at 32 minutes.
Amikacin is not metabolized, small amounts (1 to 2% of the dose) are excreted in the bile, while the remainder 98-99% is excreted in the urine via glomerular filtration. The mean human serum protein binding is 11% over a concentration range of 5 to 50 :g/mL of serum. The volume of distribution of Amikacin is 25 to 30% of body weight. Amikacin pharmacokinetics remain linear over the entire dosage range studied (0.5 :g/kg to 9 mg/kg).
Tolerance studies in normal volunteers revealed amikacin to be well tolerated locally following repeated intramuscular dosing. When given at maximally recommended doses, no ototoxicity or nephrotoxicity was reported. There is no evidence of drug accumulation with repeated dosing for 10 days when administered according to recommended doses.
A dose of 7.5 mg/kg was administered to healthy women prior to therapeutic abortion and sterilization by hysterectomy. Amikacin reached a peak concentration of 8 :g/g in the fetal lung and 16.8 :g/g in the fetal kidney. No antibiotic activity was found in the fetal liver.
FIGURE 1 MICROBIOLOGY
The antibacterial activity of amikacin was determined in vitro on 613 strains of gram-negative and gram-positive organisms.
| Test Organism (No. of Strains) | Amikacin Concentration (ug/mL)* | ||||||||
| 0.32 | 0.63 | 1.25 | 2.5 | 5 | 10 | 20 | 40 | 80 | |
| GRAM- | NEGAT | IVE | |||||||
| Escherichia coli (90) | 5.6 | 33.2 | 73.3 | 88.9 | 95.6 | 97.8 | 100 | 100 | 100 |
| Kleb. pneumoniae (46) | 2.2 | 26.1 | 73.9 | 89.1 | 97.8 | 97.9 | 100 | 100 | 100 |
| Entero. species (6) | 1.7 | 61.7 | 91.7 | 100 | 100 | 100 | 100 | 100 | 100 |
| Proteus mirabilis (34) | 0 | 2.9 | 38.2 | 55.9 | 97.0 | 100 | 100 | 100 | 100 |
| Proteus species indole (+) (30) | 6.7 | 52.3 | 73.3 | 93.3 | 100 | 100 | 100 | 100 | 100 |
| Provid. stuartii (59) | 13.6 | 40.7 | 67.8 | 91.5 | 90.3 | 100 | 100 | 100 | 100 |
| Serratia marcescens (26) | 0 | 23.1 | 88.5 | 96.2 | 96.2 | 100 | 100 | 100 | 100 |
| Salmonella species (31) | 9.7 | 29.0 | 64.5 | 100 | 100 | 100 | 100 | 100 | 100 |
| Shigella species (13) | 0 | 7.7 | 7.7 | 46.2 | 92.3 | 100 | 100 | 100 | 100 |
| Alcaligenes species (10) | 0 | 10 | 20 | 60 | 60 | 60 | 60 | 70 | 100 |
| Pseudomonas aeruginosa (104) | - | 1.0 | 2.9 | 21.2 | 68.3 | 92.3 | 97.1 | 98.1 | 100 |
| Citrobacter (5)* | 0 | 40 | 100 | 100 | 100 | 100 | 100 | 100 | 100 |
| GRAM- | POSITI | VE | |||||||
| Staph. aureus (89) (methicillin sensitive) | 20.2 | 88.8 | 96.6 | 98.9 | 100 | 100 | 100 | 100 | 100 |
| Staph. aureus (21) (methicillin resistant)** | - | 9.5 | 38.1 | 90.5 | 95.2 | 100 | 100 | 100 | 100 |
* Cumulative percentage of strains inhibited at the indicated amikacin concentration. Tests conducted on Mueller-Hinton Medium (Difco).
** Methicillin-resistant Staphyococcus aureus (MRSA) may not be completely sensitive to amikacin.
In a subsequent study, 319 different clinical isolates that were resistant to one or more aminoglycosides were collected from 76 separate sources. Among these strains were 65 Pseudomonas aeruginosa, 39 Klebsiella pneumoniae, 38 Serratia marcescens, 35 Providencia stuartii, 34 Escherichia coli, 30 Enterobacter species and 29 Proteus rettgeri. Of the 319 strains tested in vitro, 83.7% were susceptible to amikacin at a concentration of 20 :g/mL compared to 41.4% for tobramycin, 27.3% for gentamicin at 8 :g/mL and 10% for kanamycin at 20 :g/mL.
When aminoglycoside inactivation is attributed to bacterial enzymatic activity, either phosphorylation, acetylation or adenylation occurs at specific sites on the molecule. Amikacin was only inactivated by aminoglycoside acetyl transferase at the 6' amino position on the molecule. A comparison of the effect of inactivating enzymes on various aminoglycosides is listed below.
The Effect of Inactivating Enzymes on Antibacterial Activity of Aminoglycosides
| Antibiotic | Inactivating Enzymes Position on the Molecules | |||||||
| APH | ANT | AAC | ||||||
| 3'-I | 3'-II | 2" | 2' | 6' | 3-I | 3-II | 3-III | |
| Neomycin | + | + | + | + | + | |||
| Kanamycin | + | + | + | + | + | ± | ||
| Tobramycin | + | + | + | + | + | |||
| Gentamicin | + | + | ± | + | + | + | ||
| Sisomicin | + | + | + | + | + | |||
| Amikacin | + | |||||||
+ Antibiotic activity markedly reduced
± Antibiotic activity moderately reduced
APH-I and APH-II Aminoglycoside Phosphotransferase
ANT Aminoglycoside Nucleotidyltransferase
AAC-I, II and III Aminoglycoside Acetyltransferase
Disc Susceptibility Tests
Quantitative methods that require measurement of zone diameters give precise estimates of antibiotic susceptibility. One such procedure has been recommended for use with discs to test susceptibility to amikacin. Interpretation involves correlation of the diameters obtained in the disc test with MIC values for amikacin. When the causative organism is tested by the Kirby-Bauer method of disc susceptibility, a 30 mcg amikacin disc should give a zone of 17 mm or greater to indicate susceptibility. Zone sizes of 14 mm or less indicate resistance. Zone sizes of 15 to 16 mm indicate intermediate susceptibility. With this procedure, a report from the laboratory of "susceptible" indicates that the infecting organism is likely to respond to therapy. A report of "resistant" indicates that the infecting organism is not likely to respond to therapy. A report of "intermediate susceptibility" suggests that the organism would be susceptible if the infection were confined to tissues and fluids (e.g., urine), in which high antibiotic levels were attained.
TOXICOLOGY
ACUTE
The following acute LD50 values were determined for amikacin (as the sulfate).
| Species | Sex | Age | Route of Administration | No. of Animals | LD50mg/kg |
| Mouse | M | Adult | IV | 60 | 315 (297 - 334) |
| Mouse | M | Adult | IP | 50 | 2000 (1905 - 2100) |
| Mouse | M | Adult | SC | 20 | 2500 (2212 - 2825) |
| Rat | M | Adult | SC | 10 | > 3000 |
| Rat | M & F | 2 days | SC | 30 | 1700 (1619 - 1785) |
| Species | Sex | Age | Route of Administration | No. of Animals | LD50mg/kg |
| Rat | M | 14 days | SC | 40 | 1800 (1682 - 1926) |
| Rat | F | 14 days | SC | 30 | 1750 (1612 - 1899) |
| Rat | M | 20 days | SC | 50 | 2700 (2450 - 2995) |
| Rat | F | 20 days | SC | 50 | 2500 (2294 - 2725) |
Ataxia, decreased respiratory rates, muscle tremors, sedation and prostration preceded death in young rats and adult mice and similar symptoms occurred to a lesser degree in adult rats. Slight ataxia, decreased activity and general weakness was exhibited by the monkey following an injection of amikacin.
No signs of drug toxicity were observed in two female New Zealand White rabbits after intramuscular administration of amikacin at a single dose of 1000 mg/kg. Slight ataxia and slightly decreased activity for a short period were noted in two squirrel monkeys after intramuscular administration of amikacin at a single dose of 1000 mg/kg.
SUBACUTE
Amikacin, kanamycin A and gentamicin were compared for ototoxicity and nephrotoxicity in the standardized cat model. At least 5 cats were used in each group. The drugs were administered intraperitoneally, twice daily for 7 days. Amikacin was given at doses of 77, 113 and 166 mg/kg; kanamycin A at doses of 77, 93, 113, 137 and 166 mg/kg; and gentamicin at doses of 70 mg/kg. (The latter was dropped to 57 mg/kg, on the second day, because all 5 animals at this dose exhibited vestibular toxicity. No dose of amikacin or kanamycin A caused any signs of vestibular toxicity).
Evidence of cochlear toxicity, as determined grossly by the pinna response, was seen with amikacin at a dose of 332 mg/kg/day at the 3 frequencies tested (1 KHz; 2.45 KHz and 6 KHz) and only at the 2.45 KHz frequency with a 226 mg/kg/day dose. No toxicity was exhibited at a 154 mg/kg/day dose. With kanamycin A, significant cochlear toxicity was seen at doses down to 186 mg/kg/day at all frequencies tested and significant toxicity at the 2.45 KHz frequency was seen at a dose of 154 mg/kg/day. Gentamicin exhibited significant cochlear toxicity at all 3 frequencies at the 114 mg/kg/day dose.
Some histologic evidence of nephrotoxicity exhibited by one case of tubular degeneration and elevated BUN values was seen in cats receiving 332 mg/kg/day. Kanamycin A produced definite histologic evidence of nephrotoxicity at this dose and gentamicin at both 94 and 114 mg/kg/day exhibited nephrotoxicity which could not be differentiated histopathologically.
The neuromuscular blockade activity was tested on several aminoglycosides as measured by the intravenous dose producing 50% fall in blood pressure. In adult cats amikacin produced a 50% neuromuscular blockade at a single intravenous dose of 188 mg/kg ± 51, compared to 177 mg/kg ± 8 for kanamycin A and 45 mg.kg ± 16 for gentamicin.
The cardiovascular effects were measured following intravenous doses of amikacin in anesthetized dogs. No significant changes occurred in aortic pressure, heart rate, central venous pressure and left ventricular dp/dt to intravenous doses as high as 73.5 mg/kg (cumulative 103.7 mg/kg) of amikacin.
In the conscious dog, intravenous administration of amikacin (logarithmically increasing doses) up to 100 mg/kg resulted in minimal effects on aortic pressure, heart rate, electrocardiogram and behavioral effects.
CHRONIC
Amikacin was administered to 60 (30 males and 30 females) Sprague-Dawley rats and to 18 (9 males and 9 females) Beagle dogs for 100 days. The rats received doses of 20, 60 and 120 mg/kg/day subcutaneously and the dogs received doses of 30, 60 and 90 mg/kg/day intramuscularly. Kanamycin and sterile water were used as the positive and negative controls.
In both species, there was a mild decrease in erythrocytic parameters (hemoglobin, packed cell volume and red blood cell volume) with an increase in the BUN. Epithelial casts appeared in the urine with both species.
Severe anorexia occurred in 3 beagles at high doses and in 1 beagle at the intermediate dose, during administration. There was a trend with the beagles to exhibit a negativity in T waves with electrocardiographic measurements. Two beagles, at the high dose, had negative T waves approximately 30% of the PR amplitude. In both species, the most significant changes occurred in the kidney, Such as tubular degeneration, basophilia, dilatation and necrosis, were dose related. Two beagles in the high dose group exhibited focal coronary artery periateritis and focal myocarditis which may have been attributed to severe nephrotoxicity.
TERATOLOGY
MICE
There were no toxic effects on mother or fetus after subcutaneous administration of amikacin in doses of 30 mg/kg/day to 60 mg/kg/day from the sixth day to the fifteenth day of pregnancy.
RATS
Pregnant dams were subcutaneously administered 9, 30 and 60 mg/kg/day of amikacin from the sixth to the fifteenth day of pregnancy. No teratogenic effects were observed.
In a perinatal and postnatal study, amikacin was subcutaneously administered to dams, at doses of 1.5 mL/kg and 3.0 mL/kg of body weight (equivalent to 30 and 60 mg/kg), from the thirteenth day of gestation through to weaning. No adverse drug effects on fetal birth weight, survival, or growth were observed.
REFERENCES
- 1.
Bodey, Gerald P., and Steward, Dorothy:
In Vitro Studies of BB-K8, A New Aminoglycoside Antibiotic. Antimicrobial Agents and Chemotherapy 4: 186-192, August 1973.
- 2.
Bodey, Gerald P., Valdivieso, Manuel et al.:
Pharmacology of Amikacin in Humans.
Antimicrobial Agents and Chemotherapy May 1974, pp. 508-512.
- 3.
Cabana, Bernard E., and Taggart, James G.:
Comparative Pharmacokinetics of BB-K8 and Kanamycin in Dogs and Humans. Antimicrobial Agents and Chemotherapy, April 1973, pp. 478-483.
- 4.
Clarke, John T., Libke, Robert D., Regamey, Claude and Kirby, William, M.M.:
Comparative Pharmacokinetics of Amikacin and Kanamycin. Clin. Pharmacol. Ther. 15(6): 610-616, June 1974.
- 5.
Haldane, E.V., Yuce, K., and Van Rooyen, C.E.:
A New Aminoglycoside Antibiotic.
The Nova Scotia Medical Bulletin, 258-259, December 1973.
- 6.
Kawaguchi, Hiroshi, Naito, Takayuki, et al.:
BB-K8, A New Semisynthetic Aminoglycoside Antibiotic.
The Journal of Antibiotics, Vol. XXV, No. 12, December 1972, pp. 695-708.
- 7.
Kluge, Ronica M., Standiford, Harold C., et al.:
Comparative Activity of Tobramycin, Amikacin, and Gentamicin Alone and with Carbenicillin Against Pseudomonas Aeruginosa.
Antimicrobial Agents and Chemotherapy, October 1974, pp. 441-446.
- 8.
Mathias, R., Gurwith, M., Ronald, A., Stiver, G., and Berger, J.: A Clinical and Laboratory
Evaluation of Amikacin (BB-K8).
Abstract - 14th. Interscience Conference on Antimicrobial Agents and Chemotherapy, 11-13 September 1974, No. 329.
- 9.
Mitsuhashi, Susumi, Kawabe, Haruhide, et al.:
On the Antibacterial Activity of the New Antibiotic Amikacin (BB-K8). The Japanese Journal of Antibiotics 27(2):189-192, April 1974.
- 10.
Overturf, Gard D., Wilkins, Jeanette and Ressler, Ronald:
Emergence of Resistance of Providencia Stuartii to Multiple Antibiotics: Speciation and Biochemical Characterization of Providencia.
The Journal of Infectious Diseases, Vol. 129, pp. 353-357, March 1974.
- 11.
Price, K.E., and Chishold, D.R., et al.:
Microbiological Evaluation of BB-K8, A New Semisynthetic Aminoglycoside. The Journal of Antibiotics, Vol. XXV, No. 12, pp. 709-731.
- 12.
Price, K.E., Pursiano, T.A., Defuria, M.D., and Wright, G.E.:
Activity of BB-K8 (Amikacin) Against Clinical Isolates Resistant to One or More Aminoglycoside Antibiotics.
Antimicrobial Agents and Chemotherapy, Vol. 5, No. 2, pp. 143-152, February 1974.
- 13.
Reiffenstein, J.C., Holmes, S.W., Hottendorf, G.H., and Bierwagen, M.E.:
Ototoxicity Studies with BB-K8, A New Semisynthetic Aminoglycoside Antibiotic. J. Antibiot. 26:94-100, February 1973.
- 14.
Sharp, Philip, M., Saenz, Corando, A., and Martin, R. Russell:
Amikacin (BB-K8) Treatment of Multiple-Drug Resistant Proteus Infections. Antimicrobial Agents and Chemotherapy, pp. 435-438, May 1974.
- 15.
Young, Lowell, S., and Hewitt, William L.:
Activity of Five Aminoglycoside Antibiotics in vitro Against Gram-Negative Bacilli and Staphylococcus Aureus.
Antimicrobial Agents and Chemotherapy, pp. 617-625, December 1973.
- 16. Data on file at Bristol Laboratories, Syracuse, N.Y.
- 17. Data on file at Bristol Laboratories of Canada, Candiac, Que.
- 18. Unpublished Paper, Bristol Laboratories, Syracuse, N.Y.
- 19.
Daikos, G.K., et al.:
Amikacin in Treatment of Infections Caused by Gram-Negative Bacteria Resistant to Gentamicin and Other Aminoglycosides: Clinical and Bacteriologic Results. Journal of Infectious Diseases, Vol. 134 Supplement, pp. S286-S290, November 1976.
- 20.
Gooding, P.G., et al.:
A Review of Results of Clinical Trials with Amikacin.
Journal of Infectious Diseases, Vol. 134 Supplement, pp. S441-S452, November 1976.
- 21.
Khan, A.J., et al.:
Amikacin Pharmacokinetics in the Therapy of Childhood Urinary Tract Infection. Journal of Pediatrics, Vol. 58, No. 6, pp. 873-876, December 1976.
- 22.
Mathias, R.G., et al.:
Clinical Evaluation of Amikacin in Treatment of Infections Due to Gram-Negative Aerobic Bacilli.
Journal of Infectious Diseases, Vol. 134 Supplement, pp. S394-S405, November 1976.
- 23.
Mazzei, T., et al.:
Amikacin in Obstetric, Gynecologic, and Neonatal Infections: Laboratory and Clinical Studies.
Journal of Infectious Diseases, Vol. 134 Supplement, pp. S374-S379, November 1976.
- 24.
Myers, M.G., et al.:
The Effects of Gestational Age, Birth Weight and Hypoxemia on Serum Amikacin Pharmacokinetics in Infants, Unpublished.
- 25.
Sardemann, H., et al.:
Kinetics and Dose Calculations of Amikacin in the Newborn.
Clin. Pharmacol. Ther. Vol. 20, No. 1, pp. 59-66, 1977.
- 26.
Bennet, W.M.:
Aminoglycoside nephrotoxicity.
Nephron 1983; 35: 73-77.
- 27.
Campochiaro, P.A., Lim, J.I.:
Aminoglycoside toxicity in the treatment of endophthalmitis.
Arch Ophthalmol 1994;112:48-53.
- 28.
Flournoy, D.J., Robinson, M.C.:
In vitro antimicrobial susceptibilities of 349 methicillin-resistant Staphylococcus aureus isolates from veterans.
Meth Find Exp Clin Pharmacol 1990;12(8):541-544.
- 29.
Habib, N.E., Malik, T.Y., Dawidex, G.M., et al:
Toxic retinopathy secondary to repeat intravitreal amikacin and vancomycin. Eye 1994;8-6:700-702
- 30.
Hamilton-Miller, J.M.T., Shah, S.:
Activity of the semi-synthetic kanamycin B derivative, arbekacin, against methicillin-resistant Staphylococcus aureus.
J Antimicrob Chemother 1995;35(6):865-868.
- 31.
Hoitsma, A.J., Wetzels, J.F.M., Koene, R.A.P.:
Drug-induced nephrotoxicity: Aetiology, clinical features and mangement. Drug Safety 1991; 6(2): 131-147.
- 32.
Jaresko, G.S. et al.:
Risk of renal dysfunction in critically ill trauma patients receiving aminoglycosides. Clinical Pharmacy 1989; 8:43-48.
- 33.
Piguet, B., Chobaz, C., Grounauer, P.A., et al:
Toxic retinopathy relating to intravitreal injection of amikacin and vancomycin. Klin Monatsbl Augenheilkd 1996;208:358-359. (Original publication in French; English translation available).
- 34.
Talamo, J.H., D'Amico, Kenyon, K.R.:
Intravitreal amikacin in the treatment of bacterial endophthalmitis. Arch Ophthalmol 1986;104:1483-1485.