


Product Monograph - Apo-Glycopyrronium
RECENT MAJOR LABEL CHANGES
| None at time of the most recent authorization. |
|---|
TABLE OF CONTENTS
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS .................................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ..................................................................................................... 4
4 DOSAGE AND ADMINISTRATION .................................................................................... 4
4.1 Dosing Considerations .............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ......................................................... 4
4.4 Administration ......................................................................................................... 5
4.5 Missed Dose ............................................................................................................. 5
5 OVERDOSAGE ................................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................... 6
7 WARNINGS AND PRECAUTIONS ...................................................................................... 7
7.1 Special Populations .................................................................................................. 9
7.1.1 Pregnant Women ..................................................................................................... 9
7.1.2 Breast-feeding ........................................................................................................ 10
7.1.3 Pediatrics ................................................................................................................ 10
8 ADVERSE REACTIONS .................................................................................................... 10
8.1 Adverse Reaction Overview ................................................................................... 10
8.2 Clinical Trial Adverse Reactions .............................................................................. 10
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 12
8.5 Post-Market Adverse Reactions ............................................................................. 12
9 DRUG INTERACTIONS ................................................................................................... 12
9.2 Drug Interactions Overview ................................................................................... 12
9.4 Drug-Drug Interactions ........................................................................................... 13
9.5 Drug-Food Interactions .......................................................................................... 14
9.6 Drug-Herb Interactions .......................................................................................... 14
9.7 Drug-Laboratory Test Interactions ......................................................................... 14
10 CLINICAL PHARMACOLOGY ........................................................................................... 14
10.1 Mechanism of Action ............................................................................................. 14
10.2 Pharmacodynamics ................................................................................................ 14
10.3 Pharmacokinetics ................................................................................................... 15
11 STORAGE, STABILITY AND DISPOSAL............................................................................. 18
12 SPECIAL HANDLING INSTRUCTIONS .............................................................................. 19
PART II: SCIENTIFIC INFORMATION ........................................................................................ 20
13 PHARMACEUTICAL INFORMATION ............................................................................... 20
14 CLINICAL TRIALS ........................................................................................................... 21
14.1 Clinical Trials by Indication ..................................................................................... 21
Lung function ................................................................................................................... 22
Symptom Related Outcomes ............................................................................................ 25
14.2 Comparative Bioavailability Studies ....................................................................... 27
15 MICROBIOLOGY ............................................................................................................ 27
16 NON-CLINICAL TOXICOLOGY ......................................................................................... 27
17 SUPPORTING PRODUCT MONOGRAPHS ....................................................................... 29
PATIENT MEDICATION INFORMATION ................................................................................... 30
Instructions for Use of APO-GLYCOPYRRONIUM Inhaler ............................................................. 32
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-GLYCOPYRRONIUM (glycopyrronium bromide) is indicated as a long-term once-daily maintenance bronchodilator treatment in patients with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema.
APO-GLYCOPYRRONIUM is not indicated for the relief of an acute deterioration of COPD.
1.1 Pediatrics
Pediatrics (< 18 years of age): APO-GLYCOPYRRONIUM should not be used in patients under 18 years of age.
1.2 Geriatrics
Geriatrics (> 65 years of age): APO-GLYCOPYRRONIUM can be used at the recommended dose in elderly patients 65 years of age and older.
2 CONTRAINDICATIONS
APO-GLYCOPYRRONIUM is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with severe hypersensitivity to milk proteins.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Counseling by doctors on smoking cessation should be the first step in treating patients with COPD who smoke, independent of the clinical presentation i.e. chronic bronchitis (with or without airflow limitation) or emphysema. Cessation of smoking produces dramatic symptomatic benefits and has been shown to confer a survival advantage.
- Elderly patients, hepatically impaired patients, and renally impaired patients can use APO-GLYCOPYRRONIUM at the recommended dose. However, as with all renally excreted drugs, APO-GLYCOPYRRONIUM use should be monitored closely in patients with renal impairment or end stage renal disease.
- There is no experience with glycopyrronium bromide in infants and children and therefore it should not be used in this age group.
4.2 Recommended Dose and Dosage Adjustment
The recommended dosage of APO-GLYCOPYRRONIUM is the once-daily oral inhalation of the content of one 50 mcg capsule using the APO-GLYCOPYRRONIUM Inhaler. The clinical trials were conducted based on dosing in the morning.
The capsule must not be swallowed.
Dosing in special populations
Renal impairment
APO-GLYCOPYRRONIUM can be used at the recommended dose in patients with mild to moderate renal impairment. In patients with severe renal impairment or end-stage renal disease requiring dialysis APO-GLYCOPYRRONIUM should be used only if the expected benefit outweighs the potential risk (See also 7 WARNINGS AND PRECAUTIONS and 10 CLINICAL PHARMACOLOGY).
Hepatic impairment
No specific studies have been conducted in patients with hepatic impairment. Glycopyrronium bromide is predominantly cleared by renal excretion and therefore no major increase in exposure is expected in patients with hepatic impairment. No dose adjustment is required in patients with hepatic impairment.
Geriatric patients
APO-GLYCOPYRRONIUM can be used at the recommended dose in elderly patients 65 years of age and older.
Pediatric patients
APO-GLYCOPYRRONIUM should not be used in patients under 18 years of age.
4.4 Administration
APO-GLYCOPYRRONIUM is recommended for once-daily administration at the same time each day.
APO-GLYCOPYRRONIUM capsules must be administered only by the oral inhalation route and only using the APO-GLYCOPYRRONIUM Inhaler. APO-GLYCOPYRRONIUM capsules must not be swallowed (see also 5 OVERDOSAGE).
APO-GLYCOPYRRONIUM capsules must always be stored in the blister to protect from moisture, and only removed IMMEDIATELY BEFORE USE.
When prescribing APO-GLYCOPYRRONIUM, patients should be instructed on the correct use of the inhaler. Patients who do not experience improvement in breathing should be asked if they are swallowing the medicine rather than inhaling it.
4.5 Missed Dose
If a dose is missed, the next dose should be taken as soon as possible. Patients should be instructed not to take more than one dose in a day.
5 OVERDOSAGE
High doses of glycopyrronium may lead to signs and symptoms of exaggerated anticholinergic effects for which symptomatic treatment may be indicated. Such effects may include increased intraocular pressure causing pain, vision disturbances or reddening of the eye, obstipation or voiding difficulties.
In COPD patients, repeated orally inhaled administration of glycopyrronium bromide at total doses of 100 and 200 mcg once-daily for 28 days were well tolerated.
Acute intoxication by inadvertent oral ingestion of glycopyrronium bromide is unlikely due to the low oral bioavailability (about 5%).
Peak plasma levels and total systemic exposure following a single i.v. administration of 120 mcg glycopyrronium in healthy volunteers were about 50-fold and 6-fold higher, respectively, than the peak and total systemic exposure at steady-state achieved with the recommended dose (50 mcg inhaled once-daily) of glycopyrronium bromide in COPD patients and were well tolerated.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
| Oral inhalation | Inhalation powder hard capsules / contain 50 mcg glycopyrronium (as glycopyrronium bromide) | Carrageenan, FD&C Yellow 6, hypromellose, lactose monohydrate, magnesium stearate and potassium chloride |
50 mcg APO-GLYCOPYRRONIUM contains: Aluminium blister-packaged glycopyrronium as (glycopyrronium bromide) orange-transparent (cap) and colourless-transparent (body) capsules.
Each capsule contains 63 mcg glycopyrronium bromide equivalent to 50 mcg glycopyrronium. The delivered dose (the dose that leaves the mouthpiece of the APO-GLYCOPYRRONIUM Inhaler) is equivalent to 44 mcg glycopyrronium.
Each capsule also contains lactose monohydrate and magnesium stearate.
The capsule shell components are carrageenan, FD&C Yellow 6, hypromellose and potassium chloride.
The following pack type is available:
- Carton of 30 APO-GLYCOPYRRONIUM capsules (3 blister cards) and one APO-GLYCOPYRRONIUM Inhaler.
7 WARNINGS AND PRECAUTIONS
General
Not for Acute use
APO-GLYCOPYRRONIUM is a once-daily long-term maintenance treatment and is not indicated for the treatment of acute episodes of bronchospasm, i.e. as a rescue therapy.
When beginning treatment with APO-GLYCOPYRRONIUM, patients who have been taking inhaled, short-acting bronchodilators on a regular basis (e.g., four times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms.
When prescribing APO-GLYCOPYRRONIUM, the healthcare professional should also provide the patient with an inhaled, short-acting bronchodilator (i.e. short-acting beta-agonist) for treatment of COPD symptoms that occur acutely, despite regular once-daily use of APO-GLYCOPYRRONIUM.
COPD Deterioration
APO-GLYCOPYRRONIUM should not be initiated in patients with acutely deteriorating COPD, which may be a life-threatening condition. The use of APO-GLYCOPYRRONIUM in this setting is inappropriate.
COPD may deteriorate acutely over a period of hours or chronically over several days or longer. If APO-GLYCOPYRRONIUM no longer controls the symptoms of bronchoconstriction, or the patient’s inhaled, short-acting beta2-agonist becomes less effective or the patient needs more inhalation of short-acting beta2-agonist than usual, these may be markers of deterioration of disease. In this setting, a re-evaluation of the patient and the COPD treatment regimen should be undertaken at once. Increasing the daily dosage of APO-GLYCOPYRRONIUM beyond the recommended dose is not appropriate in this situation.
Excessive Use
APO-GLYCOPYRRONIUM should not be used more frequently than once daily or at higher doses than recommended. APO-GLYCOPYRRONIUM should not be administered concomitantly with other medicines containing a long-acting muscarinic antagonist, as this has not been studied, and an overdose may result.
Anticholinergic Effects
Like other anticholinergic drugs, APO-GLYCOPYRRONIUM should be used with caution in patients with narrow-angle glaucoma or urinary retention.
Worsening of Narrow-Angle Glaucoma
APO-GLYCOPYRRONIUM should be used with caution in patients with narrow-angle glaucoma. Patients should be cautioned to avoid getting the drug powder into their eyes. They should be advised that this may result in precipitation or worsening of narrow-angle glaucoma. Prescribers and patients should be alert for signs and symptoms of acute narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a physician immediately should any of these signs or symptoms develop. Miotic drops alone are not considered to be effective treatment.
Worsening of Urinary Retention
APO-GLYCOPYRRONIUM should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of prostatic hyperplasia or bladder-neck obstruction (e.g., difficulty passing urine, painful urination). Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
Cardiovascular
Cardiovascular effects, such as cardiac arrhythmias (e.g. atrial fibrillation and tachycardia), may be seen after the administration of muscarinic receptor antagonists. Patients with unstable ischaemic heart disease, left ventricular failure, history of myocardial infarction, arrhythmia (excluding chronic stable atrial fibrillation), a history of long QT syndrome or whose QTc was prolonged at screening were excluded from the clinical trials. Therefore the experience in these patient groups is limited.
APO-GLYCOPYRRONIUM should be used with caution in these patients. In some cases treatment may need to be discontinued.
Driving and Operating Machinery
No studies on the effects on the ability to drive and use machines have been performed. The occurrence of dizziness or blurred vision may influence the ability to drive and use machinery. Hence, exercise caution when driving or operating a vehicle or potentially dangerous machinery.
Immune
Hypersensitivity
Immediate hypersensitivity reactions have been reported after administration of glycopyrronium bromide. If signs suggesting allergic reactions occur, in particular, angioedema (including difficulties in breathing or swallowing, swelling of the tongue, lips, and face), urticaria, or skin rash, APO-GLYCOPYRRONIUM should be discontinued immediately and alternative therapy instituted.
Ophthalmologic
Worsening of Narrow-Angle Glaucoma (see 7 WARNINGS AND PRECAUTIONS, Anticholinergic Effects).
Renal
Patients with severe renal impairment
For patients with severe renal impairment (estimated glomerular filtration rate below 30 mL/min/1.73m2) including those with end-stage renal disease requiring dialysis, APO-GLYCOPYRRONIUM should be used only if the expected benefit outweighs the potential risk (see 10 CLINICAL PHARMACOLOGY). These patients should be monitored closely for potential adverse drug reactions.
Worsening of Urinary Retention (see 7 WARNINGS AND PRECAUTIONS; Anticholinergic Effects).
Respiratory
Paradoxical bronchospasm
As with other inhalation therapies, administration of APO-GLYCOPYRRONIUM may result in paradoxical bronchospasm that may be life-threatening. If paradoxical bronchospasm occurs, APO-GLYCOPYRRONIUM should be discontinued immediately and alternative therapy instituted.
7.1 Special Populations
Women of child-bearing potential: There are no special recommendations for women of child-bearing potential.
7.1.1 Pregnant Women
There are no data available on the use of glycopyrronium bromide in pregnant women. Therefore, APO-GLYCOPYRRONIUM should only be used during pregnancy if the expected benefit to the patient justifies the potential risk to the fetus.
7.1.2 Breast-feeding
It is not known whether glycopyrronium passes into human breast milk. However, glycopyrronium (including its metabolites) was excreted into the milk of lactating rats (See 16 NON-CLINICAL TOXICOLOGY). The use of APO-GLYCOPYRRONIUM by breast-feeding women should only be considered if the expected benefit to the woman is greater than any possible risk to the infant.
7.1.3 Pediatrics
APO-GLYCOPYRRONIUM should not be used in patients under 18 years of age.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The safety and tolerability of glycopyrronium bromide was evaluated at the recommended dose of 50 mcg once-daily in 1353 COPD patients. Of these, 842 patients have been treated for at least 26 weeks (6 months), and 351 patients for at least 52 weeks (12 months). Patients with unstable cardiac disease, long QT syndrome or QT prolongation, narrow-angle glaucoma, symptomatic prostatic hyperplasia or bladder-neck obstruction were excluded from the studies.
Adverse reactions to glycopyrronium bromide are expected to be similar in nature to other muscarinic antagonists and may include cardiovascular effects (atrial arrhythmias and tachycardia), ocular disorders (e.g. blurred vision), urinary retention, gastrointestinal disorders, dry mouth, cough and immediate hypersensitivity reactions. Adverse drug reactions to glycopyrronium bromide related to local tolerability included throat irritation, nasopharyngitis, rhinitis and sinusitis.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse drug reactions with glycopyrronium bromide reported during the first 6 months of two pooled pivotal Phase III trials of 6- and 12-months duration are listed by MedDRA system organ class (Table 2). Within each system organ class, the adverse drug reactions are ranked by frequency, with the most frequent reactions first.
Table 2 - Adverse drug reactions ≥1.0% in pooled COPD safety database
| COPD 6-month safety database | ||
|---|---|---|
| Adverse drug reactions | Glycopyrronium bromide 50 mcg once daily n=10751 N (%)2 | Placebo n=5351 N (%)2 |
| Gastrointestinal disorders | ||
| 26 (2.4) | 6 (1.1) |
| 15 (1.4) | 5 (0.9) |
| Psychiatric disorders | ||
| 11 (1.0) | 4 (0.8) |
| COPD 12-month safety database | ||
n=525 N (%) | n=268 N (%) | |
| Infections and infestations | ||
| 47 (9.0) | 15 (5.6) |
| 9 (1.7) | 2 (0.7) |
| Gastrointestinal disorders | ||
| 16 (3.0) | 5 (1.9) |
| 14 (2.7) | 1 (0.4) |
| 7 (1.3) | 1 (0.4) |
| 7 (1.3) | 2 (0.7) |
| Musculoskeletal and connective tissue disorders | ||
| 13 (2.4) | 2 (0.7) |
| 7 (1.3) | 2 (0.7) |
| 6 (1.1) | 2 (0.7) |
| Cardiac disorders | ||
| 7 (1.3) | 2 (0.7) |
| Renal and urinary tract disorders | ||
| 6 (1.1) | 0 |
| Metabolism and nutrition disorders | ||
| 6 (1.1) | 2 (0.7) |
| Respiratory, thoracic and mediastinal disorders | ||
| 6 (1.1) | 2 (0.7) |
1 n= number of patients analysed
2 N= number of patients with an adverse reaction
The most common anticholinergic adverse drug reaction was dry mouth. The majority of the reports of dry mouth were suspected to be drug related and of mild degree, none was severe. Rash was uncommon and generally mild.
8.3 Less Common Clinical Trial Adverse Reactions
The following clinical trial adverse reactions were reported in less than 1% of patients:
Cardiac disorders: palpitations
Gastrointestinal disorders: dental caries
General disorders and administration site conditions: fatigue, asthenia
Infections and infestations: cystitis
Metabolism and nutrition disorders: diabetes mellitus
Nervous system disorders: hypoesthesia
Renal and urinary disorders: urinary retention
Respiratory, thoracic and mediastinal disorders: productive cough, throat irritation, epistaxis Skin and subcutaneous tissue disorders: rash
Special populations
In elderly patients above 75 years of age the frequencies of urinary tract infection and headache were higher on glycopyrronium bromide than on placebo, with 3.0 versus 1.5% and 2.3 versus 0%, respectively.
8.5 Post-Market Adverse Reactions
The following adverse drug reactions have been reported with glycopyrronium bromide in post-marketing experience. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Immune system disorders: hypersensitivity, angioedema.
Respiratory, thoracic and mediastinal disorders: paradoxical bronchospasm, dysphonia
Skin and subcutaneous tissue disorders: pruritus
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Although no formal drug interaction studies have been performed, in clinical studies glycopyrronium bromide has been used concomitantly with other drugs commonly used to treat COPD including sympathomimetic bronchodilators, methylxanthines, oral and inhaled steroids. No safety findings were observed to contraindicate administration of these agents with glycopyrronium bromide.
In vitro, glycopyrronium was a substrate for the multidrug and toxin extrusion protein MATE1 found on renal tubule cells. Therefore the plasma levels of glycopyrronium may be increased by inhibitors of MATE1, and the plasma levels of MATE1 substrates may be increased by glycopyrronium. No clinical drug interaction studies were performed. Other in vitro studies showed that glycopyrronium bromide is not likely to inhibit or induce the metabolism of other drugs. In vitro inhibition studies demonstrated that glycopyrronium has no relevant capacity to inhibit CYP1A2, CYP2A6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP2E1 or CYP3A4/5, the efflux transporters MDR1, MRP2 or MXR. In vitro enzyme induction studies did not indicate a clinically relevant induction by glycopyrronium for any of the cytochrome P450 isoenzymes tested as well as for UGT1A1 and the transporters MDR1 and MRP2. Metabolism in which multiple enzymes are involved plays a secondary role in the elimination of glycopyrronium (see 10 CLINICAL PHARMACOLOGY). Inhibition or induction of metabolism of glycopyrronium is unlikely to result in a relevant change of systemic exposure to the drug.
9.4 Drug-Drug Interactions
Anticholinergics
There is a potential for an additive interaction with concomitantly used anticholinergic medications. Therefore, avoid co-administration of APO-GLYCOPYRRONIUM with other anticholinergic-containing drugs as this may lead to an increase in undesirable anticholinergic effects.
Cimetidine and other inhibitors of organic cation transport
In a clinical study in healthy volunteers, cimetidine, an inhibitor of organic cation transport which is thought to contribute to the renal excretion of glycopyrronium, increased total exposure (AUC) to glycopyrronium by 22% and decreased renal clearance by 23%. Based on the magnitude of these changes, no clinically relevant drug interaction is expected when glycopyrronium bromide is co-administered with cimetidine or other inhibitors of the organic cation transporter.
Table 3 - Established or Potential Drug-Drug Interactions
| Proper Name | Source of Evidence | Effect | Clinical Comment |
|---|---|---|---|
| cimetidine | CT | Increased total exposure (AUC) to glycopyrronium by 22% and decreased renal clearance by 23%. | Based on the magnitude of these changes, no clinically relevant drug interaction is expected when glycopyrronium bromide is co-administered with cimetidine or other inhibitors of the organic cation transport in patients with normal renal function. |
| Legend: CT = Clinical Trial | |||
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Glycopyrronium bromide is an inhaled long-acting muscarinic receptor antagonist (anti-cholinergic) for once- daily maintenance bronchodilator treatment of COPD. Parasympathetic nerves are the major bronchoconstrictive neural pathway in airways, and cholinergic tone is the key reversible component of airflow obstruction in COPD. Glycopyrronium bromide works by blocking the bronchoconstrictor action of acetylcholine on airway smooth muscle cells thereby dilating the airways.
Of the five known muscarinic receptor subtypes (M1-5), only subtypes M1-3 have a defined physiological function in the human lung. Glycopyrronium is a high affinity muscarinic receptor antagonist of these three receptor subtypes. It demonstrated 4- to 5-fold selectivity for the human M3 and M1 receptors over the human M2 receptor in competition binding studies. It has a rapid onset of action as evidenced by observed receptor association/dissociation kinetic parameters and the onset of action after inhalation in clinical studies.
The long duration of action can be partly attributed to sustained drug concentrations in the lungs as reflected by the prolonged terminal elimination half-life of glycopyrronium after inhalation via the inhaler in contrast to the half-life after i.v. administration (see 10 CLINICAL PHARMACOLOGY, 10.3 Pharmacokinetics, Elimination). Lung pharmacokinetic data in rats following inhalation of glycopyrronium bromide provides further evidence for this.
10.2 Pharmacodynamics
Primary Pharmacodynamic Effects
Glycopyrronium bromide increased trough FEV1 (mean of 23 h. 15 min. and 23 h. 45 min. post dose) compared to placebo at Week 12 in the 6 month and 12 month pivotal studies by 0.108L and 0.097L respectively. This effect was maintained throughout the study duration. Serial spirometry was performed over 24h post dosing in both studies and showed that glycopyrronium bromide significantly increased FEV1 over 24 hours compared to placebo.
In the pivotal studies there was a rapid onset of action within 5 minutes after inhalation of glycopyrronium bromide, with an increase in FEV1 relative to baseline ranging from 0.091 L to 0.094 L.
In vitro studies have shown that glycopyrronium bromide is a competitive, high affinity muscarinic receptor antagonist. It demonstrated 4- to 5-fold selectivity for the human M3 (pKi value: 9.59) and M1 receptors over the human M2 receptor in competition binding studies. It has a rapid onset of action as evidenced by observed receptor association/dissociation kinetic parameters and the onset of action after inhalation in clinical studies.
The contractile response of isolated rat trachea in response to a muscarinic agonist was studied following treatment with glycopyrronium bromide. Glycopyrronium bromide inhibited contraction with a rapid onset of action (≤ 15 minutes). Using an in vivo Rhesus model of muscarinic agonist-induced bronchoconstriction direct delivery of glycopyrronium bromide to the lung induced dose and time-dependent inhibition of methacholine-induced bronchoconstriction with a rapid onset of action (≤ 15 minutes). The duration of action of glycopyrronium bromide was investigated using an in vivo model of bronchoconstriction in Brown Norway rats. Muscarinic agonist-induced bronchoconstriction was markedly reduced by intratracheal instillation of glycopyrronium bromide and this effect was maintained 24h post-dose.
Secondary Pharmacodynamic Effects
The effect on heart rate and QTc interval of 120 mcg glycopyrronium administered intravenously was investigated in young healthy subjects. Peak exposures (Cmax) about 50-fold higher than after inhalation of glycopyrronium bromide 50 mcg at steady state were achieved and did not result in tachycardia or QT(c) prolongation. Mild bradycardia was observed (mean difference over 24 hours was a reduction by 2 bpm when compared to placebo), which is a known effect of low exposures to anticholinergic compounds in young healthy subjects. In a thorough QT study in 73 healthy volunteers, a single inhaled dose of glycopyrronium bromide 352 micrograms (8 times the therapeutic dose) did not prolong the QTc interval and slightly reduced heart rate (maximal effect 5.9 bpm; average effect over 24 hours 2.8 bpm) when compared to placebo. No changes in heart rate or QT(c) interval were observed with glycopyrronium bromide 200 mcg in COPD patients.
10.3 Pharmacokinetics
Table 4 - Summary of glycopyrronium bromide Pharmacokinetic Parameters in COPD patients
| Mean (Standard Deviation) | Cmax [pg/mL] | T½ (h) | AUC0-24h [pg*h/mL] | Renal Clearance (CLr) [L/h] | Volume of distribution (Vss) 3) [L] | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Mean (Standard Deviation) | Cmax [pg/mL] | T½ (h) | AUC0-24h [pg*h/mL] | Renal Clearance (CLr) [L/h] | Volume of distribution (Vss) 3) [L] | ||||||
| Single dose | 146 (109) | 52.5 (12.7) 1) | n.d. | 23.1 (7.46) 1) | 82.7 (21.7) 1) | ||||||
Multiple dose (steady state) | 166 (97.3) | 13.4 (8.02) 2) 20.8 (8.61) 2) 21.6 (3.24) 2) | 464 (213) | 17.6 (6.4) | n.d. | ||||||
Notes: n.d.= not determined;
| |||||||||||
Absorption
Following oral inhalation using the inhaler, glycopyrronium was rapidly absorbed and reached peak plasma levels at 5 minutes post dose.
The absolute bioavailability of glycopyrronium inhaled via the inhaler was estimated to be about 40%. About 90% of systemic exposure following inhalation is due to lung absorption and 10% is due to gastrointestinal absorption. The absolute bioavailability of orally administered glycopyrronium (400 mcg) was estimated to be about 5%.
Following repeated once-daily inhalation in patients with COPD, the pharmacokinetic (PK) steady-state of glycopyrronium was reached within one week of treatment. The steady-state mean peak and trough plasma concentrations of glycopyrronium for a 50 mcg once-daily dosing regimen were 166 pg/mL and 8 pg/mL, respectively. With once-daily doses of 100 and 200 mcg, steady-state exposure to glycopyrronium (AUC over the dosing interval) was about 1.4- to 1.7-fold higher than after the first dose. Urinary excretion data at steady-state compared to the first dose suggest that systemic accumulation is independent of dose in the dose range of 25 to 200 mcg.
Distribution:
After i.v. dosing, the steady-state volume of distribution (Vss) of glycopyrronium was 83 L and the volume of distribution in the terminal phase (Vz) was 376 L. The apparent volume of distribution in the terminal phase following inhalation (Vz/F) was 7310 L, which reflects the much slower elimination after inhalation. The in vitro human plasma protein binding of glycopyrronium was 38% to 41% at concentrations of 1 to 10 ng/mL. These concentrations were at least 6-fold higher than the steady state mean peak level achieved in plasma for a 50 mcg once-daily dosing regimen.
Biotransformation/Metabolism:
In vitro metabolism studies showed consistent metabolic pathways for glycopyrronium between animals and humans. No human specific metabolites were found. Hydroxylation resulting in a variety of mono- and bis-hydroxylated metabolites and direct hydrolysis resulting in the formation of a carboxylic acid derivative (M9) were seen.
In vitro investigations showed that multiple CYP isoenzymes contribute to the oxidative biotransformation of glycopyrronium. The hydrolysis to M9 is likely to be catalyzed by members from the cholinesterase family.
After inhalation, systemic exposure to M9 was on average in the same order of magnitude as the exposure to the parent drug. Since in vitro studies did not show lung metabolism and M9 was of minor importance in the circulation (about 4% of parent drug Cmax and AUC) after i.v. administration, it is assumed that M9 is formed from the swallowed dose fraction of orally inhaled glycopyrronium by pre-systemic hydrolysis and/or via first pass metabolism. After inhalation as well as i.v. administration, only minimal amounts of M9 were found in the urine (i.e. ≤ 0.5% of dose). Glucuronide and/or sulfate conjugates of glycopyrronium were found in urine of humans after repeated inhalation, accounting for about 3% of the dose.
Elimination
After i.v. administration of [3H]-labelled glycopyrronium bromide to humans, the mean urinary excretion of radioactivity in 48 h amounted to 85% of the dose. A further 5% of the dose was found in the bile. Thus, mass balance was almost complete.
Renal elimination of parent drug accounts for about 60 to 70% of total clearance of systemically available glycopyrronium whereas non-renal clearance processes account for about 30 to 40%. Biliary clearance contributes to the non-renal clearance, but the majority of non-renal clearance is thought to be due to metabolism.
Following inhalation of single and repeated once-daily doses between 50 and 200 mcg glycopyrronium by healthy volunteers and patients with COPD mean renal clearance of glycopyrronium was in the range of 17.4 and 24.4 L/h. Active tubular secretion contributes to the renal elimination of glycopyrronium. Up to 20% of the dose was found in urine as parent drug.
Glycopyrronium plasma concentrations declined in a multi-phasic manner. The mean terminal elimination half-life in healthy volunteers was much longer after inhalation (33 to 57 hours) than after intravenous (6.2 hours) and oral (2.8 hours) administration. The elimination pattern suggests a sustained lung absorption and/or transfer of glycopyrronium into the systemic circulation at and beyond 24 hours after inhalation.
Special Populations and Conditions
A population PK analysis of data in COPD patients identified body weight and age as factors contributing to inter-patient variability in systemic exposure. COPD patients with lower body weights (40 – 50 kg) had higher systemic exposure (41%) compared to those with higher body weights (90 – 100 kg). However, glycopyrronium bromide 50 mcg once-daily can be safely used in all body weight groups.
Gender, smoking status and baseline FEV1 had no apparent effect on systemic exposure.
- Pediatrics: APO-GLYCOPYRRONIUM should not be used in patients under 18 years of age.
- Geriatrics: Dose adjustment is not necessary for patients aged 65 years and older.
- Ethnic Origin: An ethnic sensitivity study conducted in Japanese and Caucasian healthy volunteers showed peak plasma exposure was on average 80% higher and total systemic exposure (AUC) and urinary excretion were 38 to 46% higher in Japanese than in Caucasian volunteers. The renal clearance (CLr) was similar for both populations. The apparent difference in total exposure may reflect differences in systemic uptake of glycopyrronium via the lungs between the two populations. APO-GLYCOPYRRONIUM 50 mcg once-daily can be safely used in the two populations. Insufficient PK data is available for other ethnicities or races.
- Hepatic Insufficiency: Clinical studies in patients with hepatic impairment have not been conducted. Glycopyrronium is cleared predominantly from the systemic circulation by renal excretion (see 10.3 Pharmacokinetics). Impairment of the hepatic metabolism of glycopyrronium is not expected to result in a clinically relevant increase of systemic exposure.
- Renal Insufficiency: Renal impairment has an impact on the systemic exposure to glycopyrronium. A moderate mean increase in total systemic exposure (AUClast) of up to 1.4-fold was seen in subjects with mild and moderate renal impairment and up to 2.2-fold in subjects with severe renal impairment and end stage renal disease. In COPD patients with mild and moderate renal impairment (estimated glomerular filtration rate eGFR≥30 mL/min/1.73m2), APO-GLYCOPYRRONIUM can be used at the recommended dose. There is no long term experience in patients with renal impairment.
11 STORAGE, STABILITY AND DISPOSAL
Store APO-GLYCOPYRRONIUM at room temperature between 15°C to 25°C. Do not store above 25°C and protect from moisture.
Keep out of the reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
- APO-GLYCOPYRRONIUM capsules should be used with the APO-GLYCOPYRRONIUM Inhaler only. The APO-GLYCOPYRRONIUM Inhaler should not be used with any other capsules.
- Capsules should always be stored in the blister and only removed from the blister immediately before use.
- Always use the new APO-GLYCOPYRRONIUM Inhaler provided with each new prescription and discard the old device.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Glycopyrronium bromide
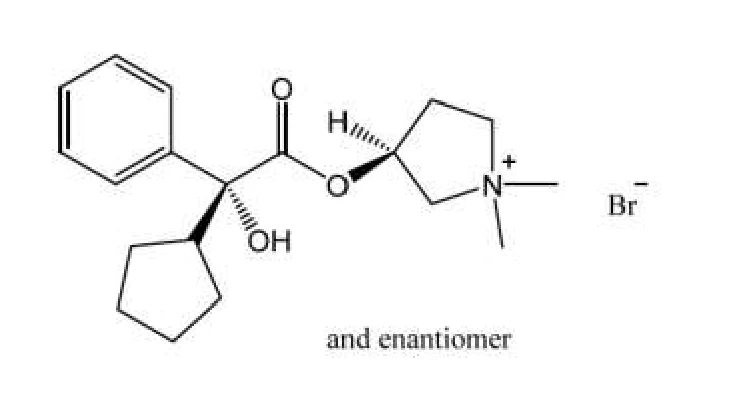
Chemical name: (3RS)-3-[(2SR)-(2-cyclopentyl-2-hydroxy-2-phenylacetyl)oxy]-1,1-dimethylpyrrolidinium bromide
Molecular formula and molecular mass: C19H28BrNO3 Salt form on anhydrous basis: 398.3 g/mol
Structural formula:
Physicochemical properties:
Description: White or almost white powder.
Solubility: Soluble in methanol, ethanol (96%) and hydrochloric acid; freely soluble in water and 1 M sodium hydroxide; very slightly soluble in acetic acid methylene chloride; practically insoluble in acetonitrile, chloroform and diethyl ether.
Melting range: Glycopyrronium bromide melts at about 193°C to 198°C
APO-GLYCOPYRRONIUM INHALATION DEVICE
The APO-GLYCOPYRRONIUM Inhaler is a plastic inhalation device used for inhaling the content of APO-GLYCOPYRRONIUM (glycopyrronium bromide) capsules. The amount of drug delivered to the lung will depend on patient factors, such as inspiratory flow rate and inspiratory time.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
The glycopyrronium bromide Phase III clinical development program consisted of two key studies (a 6-month placebo-controlled study and a 12-month placebo and active-controlled study). These studies enrolled 1888 patients with a clinical diagnosis of COPD, who were 40 years old or older, had a smoking history of at least 10 pack years, had a post-bronchodilator FEV1 <80% and ≥30% of the predicted normal value and a post-bronchodilator FEV1/FVC ratio of less than 70%.
Assessment of efficacy in trials A2304 and A2303 was based on FEV1. The primary efficacy endpoint was 24-hour post-dose trough FEV1 (defined as the average of two FEV1 measurements taken after 23 hours 10 minutes and 23 hours 45 minutes after the previous dose) after 12 weeks of treatment. Other efficacy variables included: Transition dyspnoea index (TDI), Health-related quality of life measured using the St. George’s Respiratory Questionnaire (SGRQ), time to first moderate or severe COPD exacerbation, rescue medication usage, COPD symptoms (recorded using an electronic patient diary) and FEV1, FVC and IC assessed at various time points over the treatment period.
Table 5 - Summary of patient demographics for clinical trials in COPD
| Study # | Trial design and dosage | Route of administration and duration | Study subjects‡ (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| A2303 | Randomized, double-blind, placebo-controlled, parallel- group study to assess the efficacy, safety and tolerability of glycopyrronium (50 mcg o.d.) in patients with COPD, using open label tiotropium (18 mcg o.d) as an active control | Glycopyrronium Inhalation 52 weeks | Total: n = 1060 glycopyrronium 50 mcg o.d.: n = 525 Placebo: n = 268 Open Label Tiotropium 18 mcg o.d.: n = 267 | 63.6 years (41- 87) | Male: 680 Female: 380 |
| A2304 | Randomized, double-blind, placebo-controlled, parallel group study to assess the efficacy, safety and tolerability of glycopyrronium (50 mcg o.d.) in patients with COPD | Glycopyrronium Inhalation 26 weeks | Total: n = 817 glycopyrronium 50 mcg o.d: n = 550 Placebo: n = 267 | 63.9 years (40- 91) | Male: 669 Female: 148 |
‡ Number of patients exposed to treatment or placebo
Lung function
Inhalation of glycopyrronium bromide at 50 mcg once-daily resulted in statistically significantly greater bronchodilation as measured by 24-hour post-dose trough FEV1 at 12 weeks (primary efficacy end-point) compared to placebo. The treatment difference compared to placebo was 0.108 L and 0.097 L (p<0.001) for the 6- and 12-month study respectively. Mean trough FEV1 for glycopyrronium bromide was increased by 0.113 L at week 26 in the 6-month study and 0.108 L at week 52 in the 12-month study, compared to placebo.
In both studies glycopyrronium bromide demonstrated a rapid onset of bronchodilator effect within 5 minutes after inhalation. In the 6-month study the increase in FEV1 was 0.093 L compared to placebo at 5 minutes, increasing to 0.144 L at 15 minutes after the first dose (both p<0.001). In the 12-month study the increase in FEV1 was 0.087 L at 5 minutes and 0.143 L at 15 minutes after the first dose compared to placebo (p<0.001).
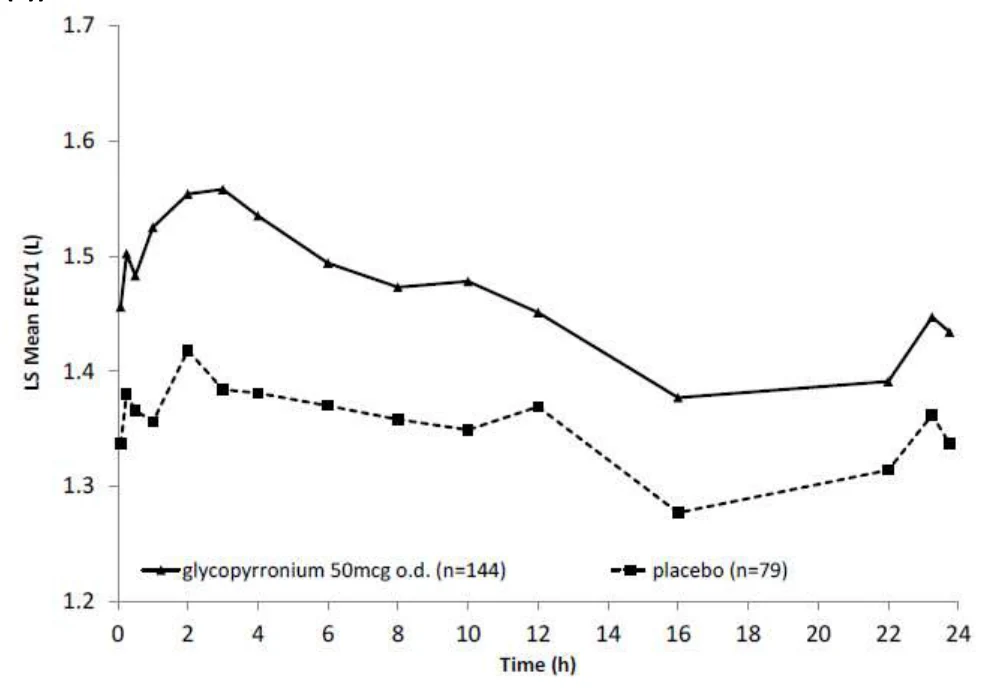
In the 6-month study serial spirometry was performed on Day 1 (Figure 1), Week 12 (Figure 2) and Week 26. In the 12 month study serial spirometry was performed on Day 1 (Figure 3), Week 12 (Figure 4) and Week 52 (Figure 5).
Serial spirometry data was used to calculate FEV1 standardized (for time) area under the curve (AUC). In the 6-month study, FEV1 AUC0-24h for glycopyrronium bromide was 0.133 L and 0.199 L compared to placebo at Week 12 and Week 26 respectively (p<0.001). In the 12-month study FEV1 AUC0-24h for glycopyrronium bromide was 0.106 L (p<0.001) compared to placebo both at 12 and at 52 weeks.
Figure 1 - Six-month pivotal study: Serial spirometry data (least square means of FEV1 (L)) after first dose
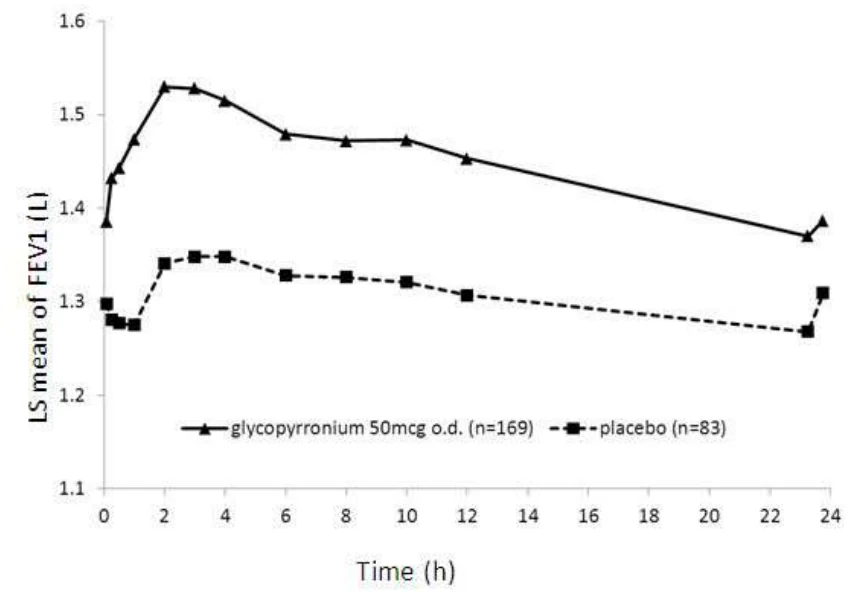
Figure 2 - Six-month pivotal study: Serial spirometry data (least square means of FEV1 (L)) at week 12
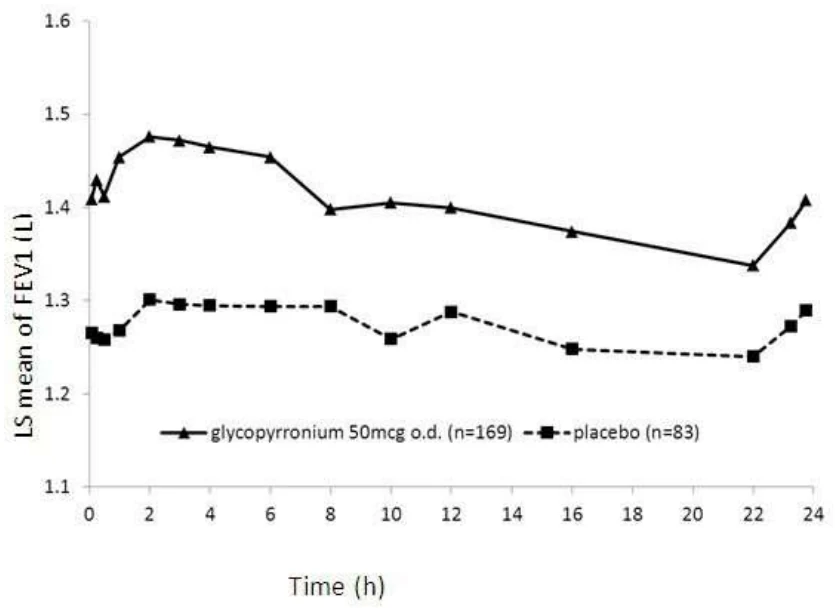
Figure 3 - Twelve-month pivotal study: Serial spirometry data (least square means of FEV1 (L)) after first dose
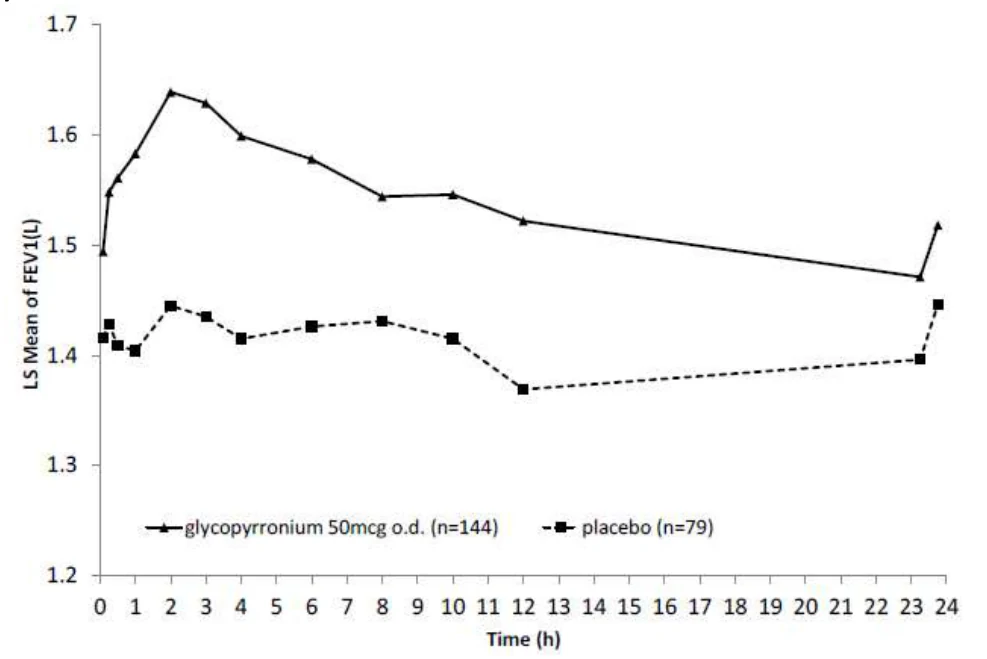
Figure 4 - Twelve-month pivotal study: Serial spirometry data (least square means of FEV1 (L)) at week 12
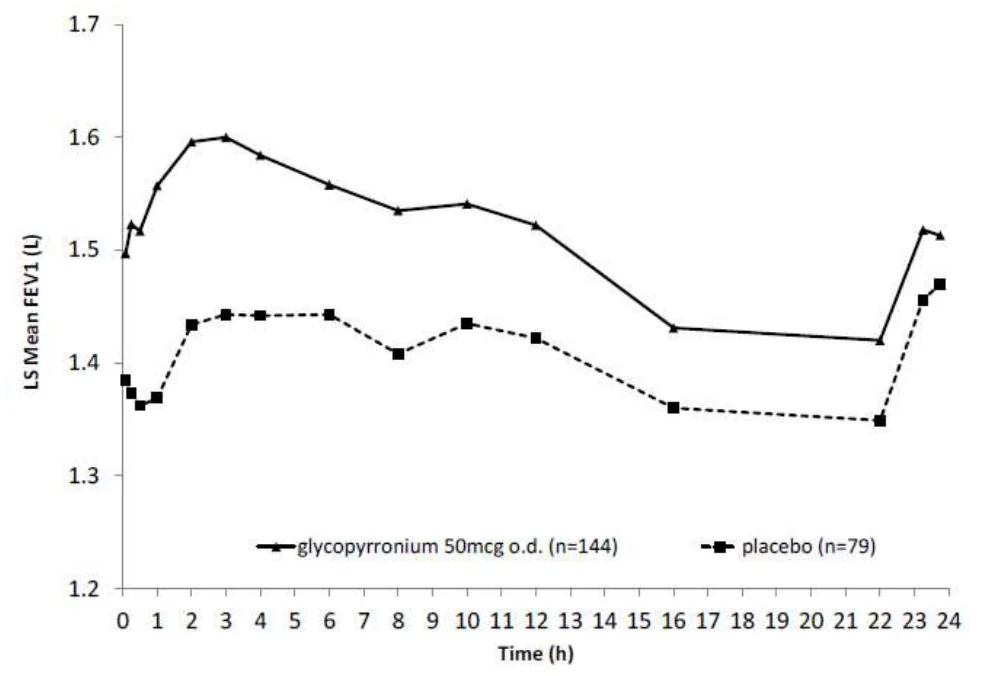
Figure 5 - Twelve-month pivotal study: Serial spirometry data (least square means of FEV1 (L)) at week 52
Glycopyrronium bromide increased mean trough FVC at Week 12 by 0.194 L and 0.183 L compared to placebo (p<0.001) in the 6- and 12-month studies respectively. Glycopyrronium bromide increased trough inspiratory capacity at Week 12 by 0.097 L and 0.129 L (p≤0.001)
compared to placebo in the 6- and 12-month studies, respectively.
Symptom Related Outcomes
Glycopyrronium bromide was shown to reduce dyspnea assessed by the Transition Dyspnea Index (TDI) focal score, improve health status assessed by the St. George’s Respiratory Questionnaire (SGRQ) total score, reduce rescue medication usage, and prolong time to first moderate or severe COPD exacerbation (moderate exacerbations were those requiring treatment with systemic corticosteroids and/ or antibiotics, severe exacerbations were those resulting in hospitalization) in the 6 month (Table 6) and 12 month (Table 7) phase III pivotal studies.
Table 6 – 6 Month pivotal study data
| Analysis of Covariance (ANCOVA) of dyspnea, health status and rescue medication usage endpoints in 6 month pivotal study | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Baseline | Treatment | Glycopyrronium bromide 50 mcg o.d. v.s. placebo -Treatment difference- | |||||||||
| Endpoint | Treatment | n | Mean | LS Mean (SE) | LS Mean (SE) | 95% CI | p-value | ||||
| TDI focal score at Week 26 | Glycopyrronium bromide 50 mcg o.d. (N=534) | 493 | 6.18 | 1.84 (0.257) | 1.04 (0.235) | (0.583, 1.504) | <0.001 | ||||
| Pbo (N=260) | 240 | 6.30 | 0.80 (0.294) | ||||||||
| SGRQ total score at Week 26 | Glycopyrronium bromide 50 mcg o.d. (N=534) | 502 | 46.11 | 39.50 (0.813) | −2.81 (0.961) | (−4.700, −0.926) | 0.004 | ||||
| Pbo (N=260) | 246 | 46.34 | 42.31 (0.992) | ||||||||
| Change from baseline in mean daily number of puffs of rescue medication over 26 Weeks | Glycopyrronium bromide 50 mcg o.d. (N=534) | 529 | 4.04 | -1.21 (0.122) | -0.46 (0.164) | (-0.784, -0.141) | 0.005 | ||||
| Pbo (N=260) | 259 | 4.05 | -0.75 (0.156) | ||||||||
Cox-regression analysis of time to first moderate or severe COPD exacerbation in 6 month pivotal study
Glycopyrronium bromide 50 mcg o.d. v.s. place
Endpoint
Treatment
n / N' (%)
Hazard Ratio
95% CI
p-value
Time to first moderate or
severe COPD exacerbation
Glycopyrronium bromide 50 mcg o.d.
(N=534)
93 / 532 (17.5)
0.69
(0.500, 0.949)
0.023
Pbo (N=260)
63 / 260 (24.2)
n = patients with a moderate or severe COPD exacerbation, N’ = number of patients included in the analysis.
Table 7 – 12 Month pivotal study data
| Analysis of Covariance (ANCOVA) of dyspnea, health status and rescue medication usage endpoints in 12 month pivotal study | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Baseline | Treatment | Glycopyrronium bromide 50 mcg o.d. v.s. placebo -Treatment difference- | |||||||||
| Endpoint | Treatment | n | Mean | LS Mean (SE) | LS Mean (SE) | 95% CI | p-value | ||||
| Transition Dyspnea Index (TDI) at Week 26 | Glycopyrronium bromide 50 mcg o.d. (N=525) | 470 | 6.06 | 2.13 (0.240) | 0.81 (0.260) | (0.299, 1.320) | 0.002 | ||||
| Pbo (N=268) | 217 | 5.95 | 1.32 (0.289) | ||||||||
| St. George’s Respiratory Questionnaire (SGRQ) at Week 52 | Glycopyrronium bromide 50 mcg o.d. (N=525) | 499 | 50.33 | 40.85 (0.854) | -3.32 (1.004) | (-5.287, -1.346) | <0.001 | ||||
| Pbo (N=268) | 248 | 50.44 | 44.16 (1.040) | ||||||||
| Change from baseline in mean daily number of puffs of rescue medication over 52 Weeks | Glycopyrronium bromide 50 mcg o.d. (N=525) | 523 | 5.21 | -1.58 (0.151) | -0.37 (0.181) | (-0.729, -0.019) | 0.039 | ||||
| Pbo (N=268) | 263 | 4.83 | -1.20 (0.184) | ||||||||
Cox-regression analysis of time to first moderate or severe COPD exacerbation in 12 month pivotal study
Glycopyrronium bromide
50 mcg o.d. v.s. placebo
Endpoint
Treatment
n / N' (%)
Hazard Ratio
95% CI
p-value
Time to first moderate or severe COPD exacerbation
Glycopyrronium bromide 50mcg o.d. (N=525)
172 / 524 (32.8)
0.66
(0.520, 0.850)
0.001
Pbo (N=268)
107 / 266 (40.2)
n = patients with a moderate or severe COPD exacerbation, N’ = number of patients included in the analysis.
Exercise tolerance and dynamic hyperinflation
In a three week cross-over study evaluating exercise tolerance during a constant work rate cycle ergometer challenge, glycopyrronium bromide increased exercise endurance time by 89 seconds, p<0.001 (an increase of 21 %) compared to placebo. Inspiratory capacity under exercise, a measure of dynamic hyperinflation, was increased by 0.200 L (p<0.001) at isotime compared to placebo.
14.2 Comparative Bioavailability Studies
An open-label, randomized, single-dose, four-period, two-treatment, two-sequence, crossover, replicate comparative bioavailability study of APO-GLYCOPYRRONIUM inhalation powder, hard capsules 50 mcg (44 mcg delivered dose) (Apotex Inc.) and PrSeebri® Breezhaler® 50 mcg (44 mcg delivered dose) (Novartis Farmacéutica SA, Spain) was conducted in 64 healthy, adult, male and female volunteers under fasting conditions.
Comparative bioavailability data from 61 subjects that were included in the statistical analysis are presented in the following table:
Glycopyrronium (1 x 50 mcg (44 mcg delivered dose)) Geometric Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (pg·h/mL) | 309.79 318.49 (25.1) | 327.08 338.30 (25.9) | 94.7 | 92.0 - 97.5 |
AUCI3 (pg·h/mL) | 461.25 474.55 (27.4) | 474.22 489.29 (28.4) | 97.3 | 93.5 - 101.2 |
Cmax (pg/mL) | 167.13 192.75 (54.0) | 197.55 240.63 (67.0) | 84.6 | 79.0 - 90.6 |
Tmax4 (h) | 0.05 (0.02 – 0.50) | 0.05 (0.02 – 0.17) | ||
T1/25 (h) | 56.22 (40.1) | 54.30 (38.3) | ||
1 APO-Glycopyrronium inhalation powder, hard capsules 50 mcg (44 mcg delivered dose) (Apotex Inc.) 2 PrSeebri® Breezhaler® 50 mcg (44 mcg delivered dose) (Novartis Farmacéutica SA, Spain) were purchased in Spain. 3 AUCI analysis includes data from 56 subjects. 4 Expressed as median (range) only. 5 Expressed as arithmetic mean (CV%) only. | ||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
Extensive data are reported in the literature for glycopyrronium bromide following single oral, intra-peritoneal or intravenous administrations to mice, rats, rabbits, dogs and cats. Further single dose investigations were also included in dose-range finding studies during an intravenous cardiovascular safety pharmacology study in dogs and a 1-week inhalation toxicity study in dogs. These studies revealed clinical signs that included mydriasis, dry nose, dry mucous mouth membranes, tachycardia, prostration, anorexia, hypertrophy of the salivary glands, and diarrhea consistent with exaggerated pharmacological effects and, at very high doses, necrotizing inflammation of the larynx and drug-induced deaths.
Repeat-dose Toxicity
Repeat dose inhalation toxicity studies were conducted in rats (up to 26 weeks) and dogs (up to 39 weeks). The effects observed in the repeated-dose studies were attributable to exacerbations of the expected pharmacological action of glycopyrronium or mild local irritation in the upper respiratory tract or adaptive response. A transient mild to moderate increases in heart rate in dogs, mydriasis in rats and a number of reversible changes including reduced secretions from the salivary and lacrimal glands in dogs and associated morphological changes in these glands and pharynx, and histopathological changes in Harderian glands in rats were related to exaggerated pharmacological effect of glycopyrronium. Findings in the respiratory tract of rats included degenerative/regenerative changes and inflammation in the nasal cavity and larynx that are consistent with mild local irritation in the upper respiratory tract. Minimal epithelial changes in the lung at the bronchioloalveolar junction were also observed in rats and are regarded as a mild adaptive response. All these findings were observed at exposures considered to be sufficiently in excess of the maximum human exposure at the therapeutic dose.
Carcinogenicity:
Carcinogenicity studies in transgenic mice using oral administration and in rats using inhalation administration revealed no evidence of carcinogenicity at systemic exposures (AUC) of approximately 53-fold higher in mice and 75-fold higher in rats than the maximum recommended dose of 50 mcg once-daily for humans.
Genotoxicity:
Genotoxicity studies did not reveal any mutagenic or clastogenic potential for glycopyrronium bromide.
Reproductive and Developmental Toxicology:
Glycopyrronium bromide was not teratogenic in rats or rabbits following inhalation administration although, significant reductions of maternal food intake and body weights were observed. Furthermore, absence and/or decreased fecal output, thinness, prominent backbone, decreased activity and aborted material/tissue at 0.4 mg/kg/day and 1.3 mg/kg/day were also observed in two rabbits.
Reproduction studies in rats regarding fertility in either males or females or pre- and post-natal development did not reveal many significant events following subcutaneous administration. There were however slight but statistically significant decreases in the number of corpora lutea and implantation sites in females at 1.5 mg/kg/day which were attributed to glycopyrronium bromide. Also, significantly lower pup body weights in the F1 generation (male, female, and genders combined) and growth during the lactation period were seen at 1.5 mg/kg/day. Diminished rates of conception and of survival at weaning in rats and reduced seminal secretion in dogs have been reported following subcutaneous administration of glycopyrronium bromide at high dose levels.
All these findings were observed at exposures in excess of the maximum human exposure.
Glycopyrronium bromide (including its metabolites) was excreted into the milk of lactating rats.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. SEEBRI® BREEZHALER® (Glycopyrronium inhalation powder hard capsules, 50 mcg glycopyrronium [as glycopyrronium bromide]), submission control 264064, Product Monograph, Novartis Pharmaceuticals Canada Inc. (OCT 28, 2022)