


Product Monograph - Incruse Ellipta
RECENT MAJOR LABEL CHANGES
Not applicable
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 4
4.1 Dosing Considerations ............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ........................................................ 5
4.4 Administration ......................................................................................................... 5
4.5 Missed Dose ............................................................................................................. 5
5 OVERDOSAGE ............................................................................................................ 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 5
7 WARNINGS AND PRECAUTIONS ................................................................................. 6
7.1 Special Populations .................................................................................................. 8
7.1.1 Pregnant Women ............................................................................................... 8
7.1.2 Breast-feeding .................................................................................................... 8
7.1.3 Pediatrics ............................................................................................................ 8
7.1.4 Geriatrics ............................................................................................................ 9
8 ADVERSE REACTIONS................................................................................................. 9
8.1 Adverse Reaction Overview ..................................................................................... 9
8.2 Clinical Trial Adverse Reactions ............................................................................... 9
8.3 Less Common Clinical Trial Adverse Drug Reactions (<1%) ................................... 10
8.5 Post-Market Adverse Reactions ............................................................................. 11
9 DRUG INTERACTIONS .............................................................................................. 11
9.2 Drug Interactions Overview ................................................................................... 11
9.4 Drug-Drug Interactions .......................................................................................... 12
9.5 Drug-Food Interactions .......................................................................................... 12
9.6 Drug-Herb Interactions .......................................................................................... 12
9.7 Drug-Laboratory Test Interactions......................................................................... 12
10 CLINICAL PHARMACOLOGY ...................................................................................... 12
10.1 Mechanism of Action ....................................................................................... 12
10.2 Pharmacodynamics .......................................................................................... 13
10.3 Pharmacokinetics ............................................................................................. 13
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 15
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 15
PART II: SCIENTIFIC INFORMATION ..................................................................................... 16
13 PHARMACEUTICAL INFORMATION .......................................................................... 16
14 CLINICAL TRIALS ...................................................................................................... 16
14.1 Clinical Trials by Indication .............................................................................. 16
COPD ................................................................................................................................ 16
15 MICROBIOLOGY ...................................................................................................... 20
16 NON-CLINICAL TOXICOLOGY .................................................................................... 21
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................... 21
PATIENT MEDICATION INFORMATION ................................................................................ 22
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
INCRUSE ELLIPTA (umeclidinium) is indicated for the long-term once-daily maintenance bronchodilator treatment of airflow obstruction in patients with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema.
INCRUSE ELLIPTA is not indicated for the relief of acute deterioration of COPD.
1.1 Pediatrics
Pediatrics (<18 years of age): INCRUSE ELLIPTA should not be used in patients under 18 years of age.
1.2 Geriatrics
Geriatrics (≥65 years of age): No dosage adjustment is required in patients 65 years of age and older.
2 CONTRAINDICATIONS
- INCRUSE ELLIPTA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- INCRUSE ELLIPTA is contraindicated in patients with severe hypersensitivity to milk proteins, see 7 WARNINGS AND PRECAUTIONS, Immune.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Counselling by healthcare professionals on smoking cessation should be the first step in treating patients with COPD who smoke, independent of the clinical presentation i.e., chronic bronchitis (with or without airflow limitation) or emphysema. Cessation of smoking produces dramatic symptomatic benefits and has been shown to confer a survival advantage.
- INCRUSE ELLIPTA should not be used more often than recommended, at higher doses than recommended, or in conjunction with other medicines containing a long-acting muscarinic antagonist, as an overdose may result.
- When beginning treatment with INCRUSE ELLIPTA, patients who have been taking oral or inhaled, short-acting bronchodilators on a regular basis (e.g., 4 times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms.
- Patients should be made aware that for optimum benefit, INCRUSE ELLIPTA must be used regularly, even when asymptomatic.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose is one inhalation of INCRUSE ELLIPTA 62.5 mcg once daily.
Geriatrics
No dosage adjustment is required in patients 65 years of age and older.
Pediatrics
INCRUSE ELLIPTA should not be used in patients under 18 years of age.
Hepatic Insufficiency
No dosage adjustment is required in patients with mild or moderate hepatic impairment. INCRUSE ELLIPTA has not been studied in patients with severe hepatic impairment (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Renal Insufficiency
No dosage adjustment is required in patients with renal impairment.
4.4 Administration
INCRUSE ELLIPTA is for oral inhalation only.
INCRUSE ELLIPTA should be administered once-daily at the same time of the day each day.
4.5 Missed Dose
If a dose is missed, the patient should be instructed to take the next dose when it is due. The patient should not be instructed to take an extra dose.
5 OVERDOSAGE
No data from clinical studies are available regarding overdose with INCRUSE ELLIPTA.
An overdose of INCRUSE ELLIPTA will likely produce signs and symptoms consistent with the known inhaled muscarinic antagonist adverse effects (e.g., dry mouth, visual accommodation disturbances and tachycardia).
There were no systemic anticholinergic adverse effects following a once-daily inhaled dose of up to 1,000 mcg umeclidinium (16 times the maximum recommended daily dose) for 14 days in subjects with COPD.
If overdose occurs, discontinue INCRUSE ELLIPTA and initiate appropriate symptomatic and/or supportive therapy.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral Inhalation | Dry powder for oral | Lactose monohydrate (which contains milk protein) and magnesium stearate |
INCRUSE ELLIPTA is supplied as a disposable grey and light green plastic inhaler containing a foil strip. Each blister on the strip contains a white powder mix of micronized umeclidinium bromide (74.2 mcg, equivalent to 62.5 mcg of umeclidinium).
The inhaler is packaged within a moisture-protective foil tray with a desiccant and a peelable lid.
INCRUSE ELLIPTA is supplied with either 30 or 7 blisters on each strip.
The actual amount of drug delivered to the lung will depend on patient factors, such as inspiratory flow rate and inspiratory time.
7 WARNINGS AND PRECAUTIONS
General
Acute bronchospasm
INCRUSE ELLIPTA is not indicated for the treatment of acute episodes of bronchospasm, i.e., as rescue therapy. INCRUSE ELLIPTA should not be initiated in patients during rapidly deteriorating or potentially life-threatening episodes of COPD. The initiation of INCRUSE ELLIPTA in this setting is not appropriate. An inhaled, short-acting bronchodilator, should be used to relieve acute symptoms such as shortness of breath. When prescribing INCRUSE ELLIPTA, the physician must also provide the patient with an inhaled, short-acting bronchodilator for treatment of acute symptoms. Patients should be advised to have their short-acting bronchodilator available at all times.
When beginning treatment with INCRUSE ELLIPTA patients who have been taking oral or inhaled, short-acting bronchodilators on a regular basis (e.g., 4 times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms.
COPD may deteriorate acutely over a period of hours or chronically over several days or longer. If INCRUSE ELLIPTA no longer controls the symptoms of bronchoconstriction, or the patient’s inhaled, short-acting bronchodilator becomes less effective or the patient needs more inhalation of a short-acting bronchodilator than usual, these may be markers of deterioration of disease. In this setting, a re-evaluation of the patient and the COPD treatment regimen should be undertaken at once. Increasing the daily dosage of INCRUSE ELLIPTA beyond the recommended dose is not appropriate in this situation.
Exacerbations may occur during treatment with INCRUSE ELLIPTA. Patients should be advised to continue treatment and seek medical advice if COPD symptoms remain uncontrolled or worsen after initiation of therapy with INCRUSE ELLIPTA.
Excessive Use
As with other inhaled bronchodilators, INCRUSE ELLIPTA should not be used more often or at higher doses than recommended.
inhalation 62.5 mcg umeclidinium (as bromide) |
INCRUSE ELLIPTA should not be administered concomitantly with other medicines containing a short- or long-acting muscarinic antagonist (e.g., ipratropium, tiotropium, glycopyrronium, aclidinium), as an overdose may result.
Anticholinergic Effects
Consistent with its antimuscarinic activity, INCRUSE ELLIPTA should be used with caution in patients with narrow-angle glaucoma or urinary retention.
Worsening of Narrow-Angle Glaucoma
INCRUSE ELLIPTA, like other antimuscarinic-containing products, should be used with caution in patients with narrow-angle glaucoma. Prescribers and patients should be alert for signs and symptoms of acute narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or coloured images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
Worsening of Urinary Retention
INCRUSE ELLIPTA, like other antimuscarinic-containing products, should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of urinary retention (e.g., difficulty passing urine, painful urination), especially in patients with prostatic hyperplasia or bladder-neck obstruction. Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
Carcinogenesis and Mutagenesis
Animal data only (see 16 NON-CLINICAL TOXICOLOGY ).
Cardiovascular
Cardiovascular effects, such as cardiac arrhythmias, e.g., atrial fibrillation and tachycardia, may be seen after the administration of muscarinic receptor antagonists, including INCRUSE ELLIPTA. Therefore, INCRUSE ELLIPTA should be used with caution in patients with severe cardiovascular disorders, particularly cardiac arrhythmias. In some cases, treatment may need to be discontinued (see 8.2 Clinical Trial Adverse Reactions).
Driving and Operating Machinery
There have been no studies to investigate the effect of INCRUSE ELLIPTA on the ability to perform tasks that require judgement, motor or cognitive skills. The occurrence of headache or blurred vision may influence the ability to drive or to use machinery.
Hepatic/Biliary/Pancreatic
Subjects with moderate hepatic impairment (Child-Pugh score of 7-9) showed no relevant increase in systemic exposure to umeclidinium (Cmax and AUC), and no relevant difference in protein binding between subjects with moderate hepatic impairment and healthy volunteers. INCRUSE ELLIPTA has not been evaluated in subjects with severe hepatic impairment.
Immune
Immediate Hypersensitivity Reactions
As with all medications, immediate hypersensitivity reactions may occur after administration of INCRUSE ELLIPTA. If signs suggesting allergic reactions (in particular, difficulties in breathing or swallowing, swelling of tongue, lips and face, urticaria, skin rash) occur, INCRUSE ELLIPTA should be discontinued immediately and alternative therapy instituted. The patient should NOT be re-challenged with INCRUSE ELLIPTA (see 2 CONTRAINDICATIONS).
There have been reports of anaphylactic reactions in patients with severe milk protein allergy after inhalation of other powder products containing lactose; therefore, patients with severe milk protein allergy should not take INCRUSE ELLIPTA (see 2 CONTRAINDICATIONS).
Ophthalmologic
Worsening of Narrow-Angle Glaucoma (see 7 WARNINGS AND PRECAUTIONS, General, Anticholinergic Effects)
Renal
Subjects with severe renal impairment (CrCl <30 mL/min) showed no relevant increase in systemic exposure to umeclidinium (Cmax and AUC), and no relevant difference in protein binding between subjects with severe renal impairment and healthy volunteers.
Respiratory
Paradoxical bronchospasm
As with other inhalation therapies, administration of INCRUSE ELLIPTA may produce paradoxical bronchospasm that may be life-threatening. Treatment with INCRUSE ELLIPTA should be discontinued if paradoxical bronchospasm occurs and alternative therapy considered if necessary.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies with INCRUSE ELLIPTA in pregnant women. INCRUSE ELLIPTA should be used during pregnancy only if the expected benefit to the mother justifies the potential risk to the fetus. Women should be advised to contact their physician if they become pregnant while taking INCRUSE ELLIPTA.
Labour and Delivery: There are no adequate and well-controlled human studies that have investigated the effects of umeclidinium during labour and delivery. INCRUSE ELLIPTA should be used during labour only if the potential benefit justifies the potential risk.
7.1.2 Breast-feeding
It is unknown whether umeclidinium is excreted in human breast milk. However, other muscarinic antagonists (including metabolites) are excreted into the milk of lactating rats. A risk to breastfed newborns/infants cannot be excluded. Therefore, the use of INCRUSE ELLIPTA by breast-feeding women should only be considered if the expected benefit to the woman is greater than any possible risk to the infant.
7.1.3 Pediatrics
Pediatrics (<18 years of age): INCRUSE ELLIPTA is not indicated for use in children and therefore should not be used in patients under 18 years of age.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Four well-controlled (12-week and 24-week) studies with INCRUSE ELLIPTA 62.5 mcg or umeclidinium 125 mcg included 810 subjects aged 65 years and older, and of those, 183 subjects were aged 75 years and older. No overall differences in safety were observed between these subjects and younger subjects, but greater sensitivity in some older individuals cannot be ruled out.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
INCRUSE ELLIPTA contains a long-acting muscarinic antagonist. Adverse reactions to INCRUSE ELLIPTA are expected to be similar in nature to other muscarinic antagonists. Adverse reactions that have been associated with other muscarinic antagonists include cardiovascular effects (atrial arrhythmias and tachycardia), ocular disorders (blurred vision), urinary retention, gastrointestinal disorders, dry mouth and cough.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The safety profile of INCRUSE ELLIPTA is primarily based on 1,663 subjects with COPD across 8 clinical studies who received at least one inhalation dose of INCRUSE ELLIPTA 62.5 mcg or umeclidinium 125 mcg (mean age 62.7, 89% white, 65% male; across all treatment arms, including placebo). In the four pivotal randomized, double-blind, placebo or active comparator-controlled efficacy clinical studies, 1,185 subjects received umeclidinium for up to 24 weeks, of which 487 subjects received the recommended dose of INCRUSE ELLIPTA 62.5 mcg. In a randomized, double-blind, placebo-controlled long-term safety study, 227 subjects received umeclidinium 125 mcg for up to 52 weeks. Patients were excluded from clinical studies if they had clinically significant cardiovascular abnormalities that were uncontrolled or a significant ECG finding from the 12-lead ECG conducted at the study entry.
12-week and 24-week pivotal studies
The incidence of adverse events presented in Table 2 is based upon two pivotal placebo-controlled efficacy studies: one 12-week study and one 24-week study. Adverse events in subjects receiving INCRUSE ELLIPTA reported with a frequency of equal to or greater than 1%, and exceeding the rate in subjects receiving placebo are listed in Table 2.
Table 2 Adverse Events With INCRUSE ELLIPTA With ≥1% Incidence and More Common Than with Placebo in Subjects with Chronic Obstructive Pulmonary Disease
8.3 Less Common Clinical Trial Adverse Drug Reactions (<1%)
Cardiac disorders: atrial fibrillation.
Gastrointestinal disorders: constipation.
Infections and Infestations: sinusitis.
52-week study
In a long-term safety study, 336 subjects (n=227 umeclidinium 125 mcg, n=109 placebo) were treated for up to 52 weeks with umeclidinium 125 mcg or placebo. The demographic and baseline characteristics of the long-term safety study were similar to those of the efficacy studies. Patients with an abnormal/significant ECG finding or from 24-hour Holter monitoring finding during the study withdrew from the study.
The adverse events reported in subjects receiving umeclidinium 125 mcg with a frequency of equal to or greater than 1% and exceeding the rate in subjects receiving placebo in this study were: upper respiratory tract infection, pharyngitis, pneumonia, lower respiratory tract infection, rhinitis, headache, dizziness, sinus headache, cough, back pain, arthralgia, pain in extremity, neck pain, myalgia, nausea, dyspepsia, diarrhea, rash, depression, vertigo, nasopharyngitis, supraventricular extrasystoles, sinus tachycardia, supraventricular tachycardia, rhythm idioventricular, and urinary tract infection.
| Adverse Event | INCRUSE ELLIPTA 62.5 mcg (n=487) % | Placebo (n=348) % |
|---|---|---|
| Infections and Infestations | ||
| Nasopharyngitis | 8 | 7 |
| Upper respiratory tract infection | 5 | 4 |
| Viral upper respiratory tract infection | 1 | <1 |
| Pharyngitis | 1 | <1 |
| Respiratory, thoracic, and mediastinal disorders | ||
| Cough | 3 | 2 |
| Injury, poisoning and procedural complications | ||
| Contusion | 1 | <1 |
| Musculoskeletal and Connective Tissue Disorders | ||
| Arthralgia | 2 | 1 |
| Myalgia | 1 | <1 |
| Gastrointestinal disorders | ||
| Abdominal pain upper | 1 | <1 |
| Toothache | 1 | <1 |
| Cardiac disorders | ||
| Tachycardia | 1 | <1 |
12-week additional studies
The safety of INCRUSE ELLIPTA in combination with an inhaled corticosteroid/long-acting beta2-adrenergic agonist (ICS/LABA) was evaluated in four 12-week clinical trials. A total of 1,640 subjects with COPD across four 12-week, randomized, double-blind clinical trials received at least 1 dose of INCRUSE ELLIPTA (62.5 mcg) or placebo administered once daily in addition to background ICS/LABA (mean age: 64 years, 88% white, 65% male across all treatments) (see 10.2 Pharmacodynamics, Clinical Pharmacology). Two trials evaluated INCRUSE ELLIPTA in combination with fluticasone furoate/vilanterol (FF/VI) 100 mcg/25 mcg administered once daily; and 2 trials evaluated INCRUSE ELLIPTA administered once daily in combination with fluticasone propionate/salmeterol (FP/SAL) 250 mcg/50 mcg administered twice daily. Adverse reaction profiles seen in these four 12-week studies were similar to that observed in pivotal studies and the 52-week long-term study. Adverse reactions occurring with INCRUSE ELLIPTA in combination with an ICS/LABA, at an incidence of greater than or equal to 1% and exceeding ICS/LABA alone were oropharyngeal pain and dysgeusia.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified from post-approval use of INCRUSE ELLIPTA. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Nervous System Disorders: dysgeusia (common)
Immune System Disorders: hypersensitivity reactions including: rash, urticaria and pruritus (uncommon); anaphylaxis (rare), angioedema (rare)
Eye Disorders: vision blurred (unknown), eye pain (unknown), glaucoma (unknown)
Respiratory, thoracic and mediastinal disorders: Dysphonia (rare), Oropharyngeal pain (rare)
Renal and Urinary Disorders: urinary retention (unknown), dysuria (unknown)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Metabolic and transporter based drug interactions
Umeclidinium is a substrate of cytochrome P450 2D6 (CYP2D6); however umeclidinium pharmacokinetics were not significantly affected in a population of CYP2D6 poor metabolizers (see 10.3 Pharmacokinetics, Metabolism).
Umeclidinium is a substrate of P-glycoprotein (P-gp). The effect of the moderate P-gp transporter inhibitor verapamil (240 mg once daily) on the steady-state pharmacokinetics of umeclidinium was assessed in healthy volunteers. An approximately 1.4-fold increase in umeclidinium AUC was observed with no effect on Cmax. A decrease in blood potassium, an increase in QTc interval and an increased number of supraventricular tachycardia events occurred with co-administration with verapamil (see 10.3 Pharmacokinetics, Metabolism).
Clinically significant interactions mediated by umeclidinium at clinical doses are considered unlikely due to the low plasma concentrations achieved after inhaled dosing.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 3 Established or Potential Drug-Drug Interactions
| Drug Class | Ref | Effect | Clinical comment |
| Anticholinergics | T | There is potential for an interaction with concomitantly used anticholinergic medications. | Avoid co-administration with other anticholinergic-containing drugs. |
| Inhibitors of P-gp | CT | May alter the systemic exposure to umeclidinium resulting in pharmacodynamics effects. | An approximately 1.4-fold increase in umeclidinium AUC was observed. No effect of verapamil was observed on umeclidinium Cmax. No dose adjustment is warranted. |
| CYP2D6 inhibitors | T | May alter systemic exposure to umeclidinium resulting in pharmacodynamics effects. | Umeclidinium pharmacokinetics were not significantly affected in a population of CYP2D6 poor metabolizers. No dose adjustment is warranted. |
Abbreviations: CT=Clinical Trial; T=Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been evaluated. The oral bioavailability of umeclidinium is <1%, therefore no food effect study was performed.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been evaluated.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been evaluated.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
INCRUSE ELLIPTA is a once-daily inhaled long-acting muscarinic receptor antagonist (LAMA), also referred to as a long-acting anticholinergic. It is a quinuclidine derivative that is a muscarinic receptor antagonist with activity across multiple muscarinic cholinergic receptor subtypes. Following oral inhalation, it acts locally on airways to produce bronchodilation. Umeclidinium exerts its 24-hour bronchodilatory activity by competitively inhibiting the binding of acetylcholine with muscarinic acetylcholine receptors on airway smooth muscle. It demonstrates slow reversibility at the human M3 muscarinic receptor subtype in vitro and a long duration of action in vivo when administered directly to the lungs in pre-clinical models.
10.2 Pharmacodynamics
Cardiac Electrocardiography
The effect of umeclidinium 500 mcg (8X therapeutic dose) on the ECG parameters was investigated in 103 healthy subjects in a double-blind, randomized, placebo- and active- controlled, incomplete block, crossover study. Following repeat doses of umeclidinium 500 mcg once daily for 10 days, no clinically relevant effect on prolongation of QTcF interval (QTcF=QT/RR0.33) was observed. UMEC 500 mcg was associated with small positive mean differences from placebo in heart rate from 4 to 24 h, inclusive, with a maximum mean difference of 2.1 bpm (90% CI: 0.7, 3.5) at 8 h.
Clinical Pharmacology
Four 12-week additional trials (Combination with an ICS/LABA trials)
The efficacy of INCRUSE ELLIPTA in combination with an ICS/LABA was evaluated in four 12-week randomized, double-blind, parallel group trials in subjects with COPD. Subjects were randomized to INCRUSE ELLIPTA 62.5 mcg + ICS/LABA or placebo + ICS/LABA. Entry criteria for subjects enrolled in these trials were similar to those described in pivotal clinical studies. The primary endpoint for these trials was change from baseline in trough (pre-dose) FEV1 at Day 85 (defined as the mean of the FEV1 values obtained at 23 and 24 hours after the previous dose on Day 84). Baseline FEV1 was measured while subjects were on background ICS/LABA.
Two trials randomized subjects to INCRUSE ELLIPTA 62.5 mcg + FF/VI 100/25 mcg administered once daily or placebo + FF/VI 100/25 mcg administered once daily. The results showed that patients treated with INCRUSE ELLIPTA 62.5 mcg + FF/VI 100/25 mcg had statistically significant greater mean changes from baseline in trough FEV1 relative to placebo + FF/VI 100/25 mcg (124 mL; 95% CI: 93, 154 and 122 mL; 95% CI: 91, 152).
Similarly, two trials randomized subjects to INCRUSE ELLIPTA 62.5 mcg + FP/SAL 250/50 mcg or placebo + FP/SAL 250/50 mcg. The treatments with INCRUSE ELLIPTA and placebo were administered once daily, while the FP/SAL treatment was administered twice daily. The results showed that patients treated with INCRUSE ELLIPTA 62.5 mcg + FP/SAL 250/50 mcg had statistically significant greater mean changes from baseline in trough FEV1 relative to placebo + FP/SAL 250/50 mcg (147 mL; 95% CI: 107, 187 and 127 mL; 95% CI: 89, 164).
In all four trials, the improvements of trough FEV1 were supported by secondary efficacy endpoint of 0-6 hour weighted mean FEV1 at Day 84; however, there were no differences in SGRQ among treatment groups, and the short duration of these studies and limited number of exacerbation events, preclude any conclusion regarding additional effect of INCRUSE ELLIPTA on COPD exacerbation.
10.3 Pharmacokinetics
Table 4 Summary of Umeclidinium Pharmacokinetic Parameters in Healthy Subjects
| Tmax (h) | t½ (h) | |
|---|---|---|
| Median (range) | Geometric Mean (CV%) | |
| Umeclidinium 500 mcg | 0.1 (0.08, 0.23) | 25.9 (0.1) |
Table 5 Summary of Umeclidinium (Cmax and AUC(0-24)) in Subjects with COPD (Geometric Mean [95% CI])
| INCRUSE ELLIPTA 62.5 mcg | Cmax (pg/mL) | AUC(0-24) (pg.h/mL) |
|---|---|---|
| Umeclidinium 62.5 mcg1 | 70 (67, 74) | 318 (303, 334) |
1Population pharmacokinetic analyses across 2 trials in subjects with COPD who received INCRUSE ELLIPTA (DB2116975).
Absorption
Following inhaled administration of umeclidinium in healthy volunteers, Cmax occurred at 5 to 15 minutes. The absolute bioavailability of inhaled umeclidinium was on average 13% of the dose, with negligible contribution from oral absorption. Following repeat dosing of inhaled umeclidinium, steady state was achieved within 7 to 10 days with 1.5 to 2-fold accumulation.
Distribution
Following intravenous administration to healthy subjects, the mean volume of distribution was 86 L. In vitro plasma protein binding in human plasma was on average 89%.
Metabolism
In vitro studies showed that umeclidinium is metabolized principally by the cytochrome P450 enzyme CYP2D6 and is a substrate for the P-gp transporter. The primary metabolic routes for umeclidinium are oxidative (hydroxylation, O-dealkylation) followed by conjugation (e.g., glucuronidation, etc.), resulting in a range of metabolites with either reduced pharmacological activity or for which the pharmacological activity has not been established. Systemic exposure to the metabolites is low.
Elimination
Plasma clearance following intravenous administration was 151 L/hour. Following intravenous administration, approximately 58% of the administered radio-labelled dose (or 73% of the recovered radioactivity) was excreted in feces and 22% of the administered radio-labelled dose (27% of recovered radioactivity) in urine. The excretion of the drug-related material in the feces following intravenous dosing indicated secretion into the bile. Following oral administration to healthy male subjects, total radioactivity was excreted primarily in feces (92% of the administered radio-labelled dose). Less than 1% of the orally administered dose was excreted in urine, suggesting negligible absorption following oral administration. Umeclidinium plasma elimination half-life following inhaled dosing for 10 days averaged 19 hours, with 3% to 4% drug excreted unchanged in urine at steady-state.
Special Populations and Conditions
- Geriatrics: A population pharmacokinetic analysis showed that pharmacokinetics of umeclidinium are similar between COPD patients 65 years and older and those younger than 65 years of age.
- Gender: A population pharmacokinetic analysis showed that no dose adjustment is required for umeclidinium based on the effect of gender.
- Ethnic Origin: A population pharmacokinetic analysis showed that no dose adjustment is required for umeclidinium based on the effect of race.
Hepatic Insufficiency: The pharmacokinetics of umeclidinium have been evaluated in subjects with moderate hepatic impairment (Child-Pugh score of 7-9). There was no evidence of an increase in systemic exposure to umeclidinium (Cmax and AUC), and no evidence of altered
- protein binding between subjects with moderate hepatic impairment and healthy volunteers. Umeclidinium has not been evaluated in subjects with severe hepatic impairment.
- Renal Insufficiency: The pharmacokinetics of umeclidinium have been evaluated in subjects with severe renal impairment (creatinine clearance < 30 mL/min). Umeclidinium systemic exposure was not significantly increased (10% for AUC), and there was no evidence of altered protein binding between subjects with severe renal impairment and healthy volunteers.
11 STORAGE, STABILITY AND DISPOSAL
Do not store above 30°C. Store in a dry place away from direct heat or sunlight.
Keep out of sight and reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
INCRUSE ELLIPTA is provided in a foil laminate tray containing a desiccant sachet. The tray is sealed with a peelable foil lid, which together provide moisture protection, and should only be opened when it is ready to be used for the first time. Once the tray is opened, the desiccant package should be discarded.
Patients should be instructed to write the date the inhaler should be discarded on the label in the space provided. The date should be added as soon as the inhaler has been removed from the tray.
INCRUSE ELLIPTA should be safely discarded when the dose counter reads “0” or 6 weeks after it was removed from the foil tray, whichever comes first.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: umeclidinium bromide
Chemical name: 1-[2-(benzyloxy)ethyl]-4-(hydroxydiphenylmethyl)-1-azoniabicyclo[2.2.2]octane bromide
Molecular formula and molecular mass: C29H34NO2•Br 508.5
Structural formula:
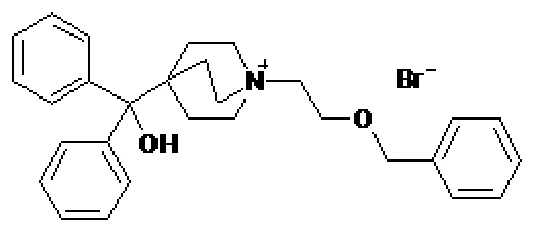
Physicochemical properties: umeclidinium bromide is a white powder. It is slightly soluble in water.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
COPD
Table 6 Summary of Trial Design and Patient Demographics for Clinical Trials
| Study # | Trial design, route of administration and study duration | Treatment and Dosage | Study Subjects Mean age (Range) Gender (%) | Primary Efficacy Endpoint |
| AC4115408 | 12-Week, Randomized, Double-Blind, Placebo-Controlled, Parallel-Group Study to Evaluate the Efficacy and Safety of INCRUSE ELLIPTA Delivered Once-Daily via a Novel Dry Powder Inhaler in Subjects with Chronic Obstructive Pulmonary Disease | INCRUSE ELLIPTA (UMEC 62.5 mcg) UMEC 125 mcg Placebo | Total: 206 63 years (41-86) Male: 62% Female: 38% | Trough FEV1 at Day 85 |
| Study # | Trial design, route of administration and study duration | Treatment and Dosage | Study Subjects Mean age (Range) Gender (%) | Primary Efficacy Endpoint |
| DB2113373 | 24-week, multicenter, randomized, double-blind, placebo-controlled, parallel-group study to evaluate the efficacy and safety of ANORO ELLIPTA inhalation powder and the individual components delivered once-daily via a novel dry powder inhaler in subjects with COPD | INCRUSE ELLIPTA (UMEC 62.5 mcg) ANORO ELLIPTA (UMEC/VI 62.5/25 mcg) VI 25 mcg Placebo | Total: 1532 63 years (40-93) Male: 71% Female: 29% | Trough FEV1 at Day 169 |
Abbreviations: UMEC = umeclidinium, VI = vilanterol
Trial Design and Study Demographics
The efficacy and safety of INCRUSE ELLIPTA (umeclidinium 62.5 mcg once daily) was evaluated in two pivotal randomized, double-blind, parallel-group, placebo-controlled clinical studies in adult subjects with COPD associated with chronic bronchitis and/or emphysema; a 12-week study (AC4115408) and a 24-week study (DB2113373).
AC4115408 was a 12-week placebo-controlled study, and DB2113373 was a 24-week placebo-controlled study. Both trials had similar inclusion/exclusion criteria and concomitant medications. For AC4115408, the primary efficacy endpoint was trough FEV1 at Day 85 (Week 12), and the secondary efficacy endpoints were weighted mean FEV1 over 0-6 hours at Day 1 and at Weeks 4 and 12 and serial FEV1 at Day 1 and Week 12. For DB2113373, the primary efficacy endpoint was trough FEV1 at Day 169 (Week 24), and the secondary efficacy endpoint was weighted mean FEV1 over 0-6 hours at Day 168 (Week 24). Transitional Dyspnea Index (TDI) focal score, St. George’s Respiratory Questionnaire (SGRQ) and daily rescue medication use were assessed as other efficacy endpoints in these trials.
A total of 1,738 subjects were randomized and received treatments from pivotal studies AC4115408 and DB2113373 (Table 6). The subjects had a clinical diagnosis of COPD, were 40 years of age or older, had a history of smoking equal to or greater than 10 pack-years, had moderate-to-very severe airflow obstruction (a post-salbutamol FEV1 ≤ 70% of predicted normal values, and a ratio of FEV1/FVC < 0.7), and dyspnea (a Modified Medical Research Council (mMRC) score ≥ 2). Concurrent use of systemic corticosteroids, long-acting bronchodilators, including theophyllines, was not allowed and previous use of umeclidinium was not allowed. Concurrent use of inhaled corticosteroids (ICS) at a stable dose and study-provided rescue salbutamol were allowed. Subjects with a current diagnosis of asthma, α 1-antitrypsin deficiency, any clinically significant uncontrolled disease, a clinically significant ECG or clinically significant laboratory finding, or a lower respiratory tract infection or recent COPD exacerbation were excluded.
The majority of the 904 patients receiving umeclidinium or placebo in the AC4115408 and DB2113373 trials were male (69%), white (85%), with a mean age of 63.3 years. At baseline, the mean post-bronchodilator FEV1 was 1355 mL (GOLD II [45%], GOLD III [43%], GOLD IV [13%]). Mean beta2-agonist responsiveness was 13.5% of baseline (137 mL).
Study Results
Lung Function
The pivotal placebo-controlled study (AC4115408) evaluated the efficacy of INCRUSE ELLIPTA compared with placebo, administered once daily. At week 12, INCRUSE ELLIPTA statistically significantly increased the change from baseline in trough FEV1 compared with placebo (Table 7). INCRUSE ELLIPTA also provided a statistically significant improvement compared with placebo in change from baseline in weighted mean FEV1 over 0-6 hours post-dose at Day 1 and Day 84 [125 mL (95% CI=83 mL to 166 mL, p<0.001) and 166 mL (95% CI=94 mL to 239 mL, p<0.001), respectively].
Table 7 Primary efficacy endpoint at Week 12 (Day 85) for Treatment with INCRUSE ELLIPTA (62.5 mcg) in AC4115408
| Trough FEV1 (mL) at Week 12 (Day 85) | |||
|---|---|---|---|
| Difference from Placebo | |||
| Treatment Difference | (95% CI) | p-value | |
| INCRUSE ELLIPTA 62.5 mcg vs Placebo | 127 | (52,202) | <0.001 |
Abbreviations: CI= confidence interval; FEV1= forced expiratory volume in 1 second; mL=milliliters
Serial FEV1 improvements were statistically significant compared with placebo at each timepoint and were sustained over 24 hours on Day 1 and Day 84.
The pivotal placebo-controlled study (DB2113373) evaluated the efficacy of INCRUSE ELLIPTA compared with placebo, administered once daily. At week 24, INCRUSE ELLIPTA statistically significantly increased the change from baseline in trough FEV1 compared with placebo (Table 8). INCRUSE ELLIPTA also provided a statistically significant improvement compared with placebo in change from baseline in weighted mean FEV1 over 0-6 hours post-dose at week 24 (see Table 8).
Table 8 Primary and Secondary Efficacy Endpoints at Week 24 for Treatment with INCRUSE ELLIPTA (62.5 mcg) in DB2113373
| Primary Endpoint | |||||||
|---|---|---|---|---|---|---|---|
| Trough FEV1 (mL) at Day 169 | |||||||
| Treatment Difference | 95% CI | p-value | |||||
| INCRUSE ELLIPTA 62.5 mcg vs Placebo | 115 | (76,155) | <0.001 | ||||
| Secondary Endpoint | |||||||
| 0-6 Hr Weighted Mean FEV1 (mL) at Day 168 | |||||||
| Treatment Difference | 95% CI | p-value | |||||
| INCRUSE ELLIPTA 62.5 mcg vs Placebo | 150 | (110,190) | <0.001 | ||||
| Abbreviations: CI=confidence interval; FEV1=forced expiratory volume in 1 second; mL=milliliters | |||||||
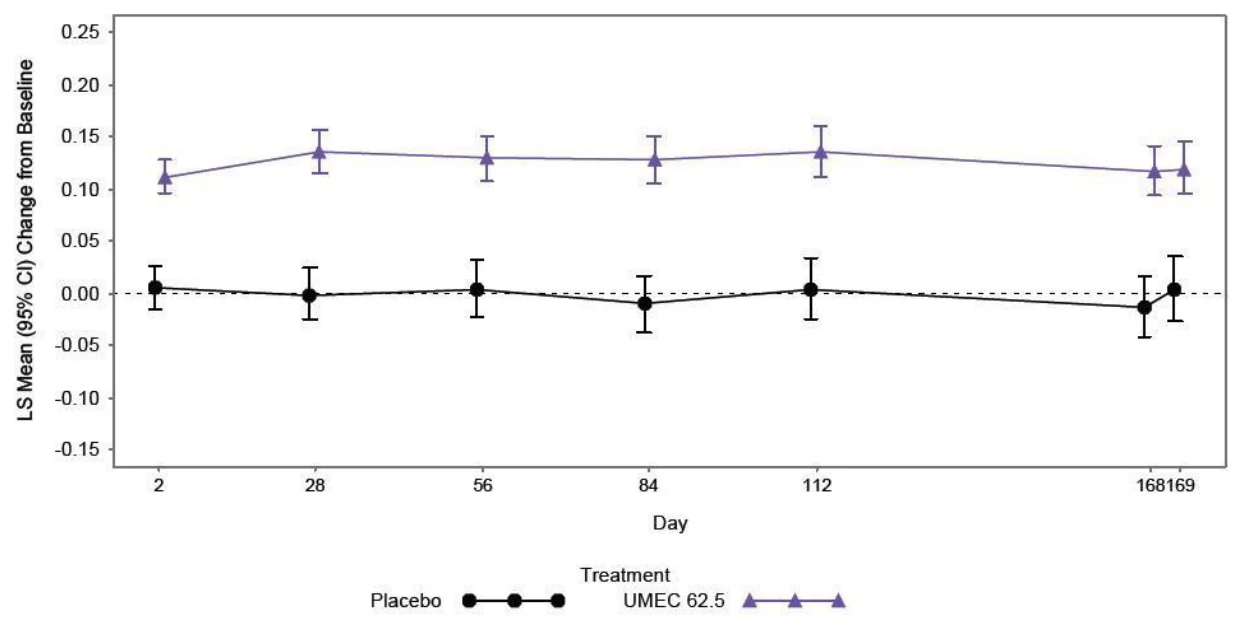
Greater bronchodilation with INCRUSE ELLIPTA compared with placebo was evident after the first day of treatment and improvement in lung function was maintained over the 24-week treatment period (Figure 1).
Figure 1 Least Squares (LS) Mean (95% CI) Change from Baseline in Trough FEV1 (L) (DB2113373: Intent-to-Treat Population)
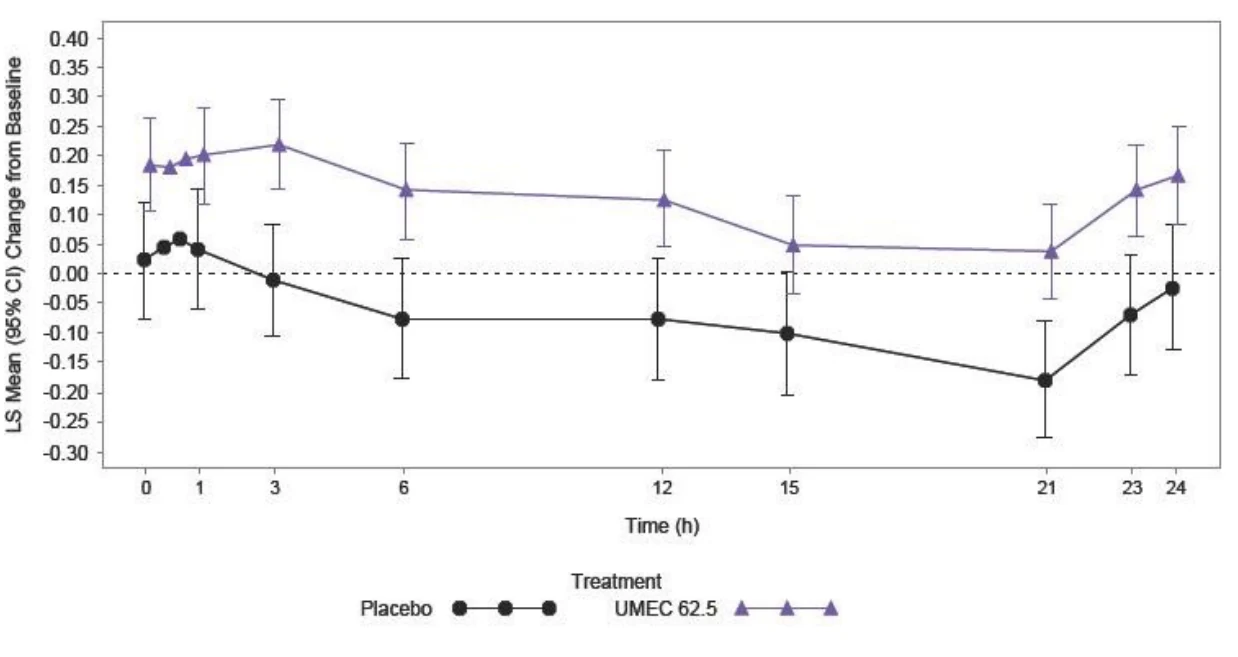
Serial spirometric evaluations throughout the 24-hour dosing interval were performed in a subset of subjects (n = 54, INCRUSE ELLIPTA 62.5 mcg; n = 36, placebo) at Days 1, 84, and 168. The median time to onset on Day 1, defined as a 100 mL increase from baseline in FEV1 was 56 minutes in subjects receiving INCRUSE ELLIPTA. Improvement in lung function from baseline was maintained for 24 hours after dosing (see Figure 2) and was consistent over Days 1, 84, and 168.
Figure 2 Least Squares (LS) Mean Change from Baseline in FEV1 (L) Over Time (0-24 hr) on Day 168 (DB2113373: Subset Population)
Symptom Related Outcomes
In the pivotal placebo-controlled study, AC4115408, INCRUSE ELLIPTA demonstrated an improvement when compared with placebo in reducing shortness of breath, as measured by the TDI focal score at Week 12 (Day 84), although the improvement was not statistically significant (1.0 units; 95% CI=0.0 to 2.0). The percentage of patients that responded with minimum clinically important difference (MCID) of ≥1 unit TDI focal score at Week 12 (Day 84) for INCRUSE ELLIPTA was 38% (24/64) compared with 15% (8/53) for placebo.
In the pivotal placebo-controlled Study DB2113373, INCRUSE ELLIPTA demonstrated an improvement when compared with placebo in reducing shortness of breath, as measured by the TDI focal score at Week 24 (Day 168) (1.0 units; 95% CI=0.5 to 1.5). The percentage of patients that responded with MCID of ≥1 unit TDI focal score at Week 24 (Day 168) for INCRUSE ELLIPTA was 53% (207/394), compared with 41% (106/260) for placebo.
Health-related quality of life was measured using St. George’s Respiratory Questionnaire (SGRQ) in both pivotal trials. In Study AC4115408 following 12 weeks of treatment, the mean difference from baseline in SGRQ total score between INCRUSE ELLIPTA and placebo was -7.90 units (95% CI=-12.20 to -3.60). More patients treated with INCRUSE ELLIPTA had an improvement in SGRQ total score greater than the MCID (4 units) compared to placebo (44% vs. 26%).
In Study DB2113373, the mean difference in change from baseline in SGRQ total score between INCRUSE ELLIPTA and placebo at Day 28 and Day 168 was -5.15 units (95% CI=-6.89 to -3.4) and -4.69 units (95% CI=-7.07 to -2.31), respectively. Improvements from baseline with INCRUSE ELLIPTA were seen in all 3 SGRQ domains (symptoms, activities and impact; mean change from baseline on Day 168 was -10.97, -5.62 and -6.30 units, respectively). More patients treated with INCRUSE ELLIPTA had an improvement in SGRQ total score greater than the MCID (4 units) compared to placebo (44% vs. 34%).
In Study AC4115408, patients treated with INCRUSE ELLIPTA required less rescue salbutamol than those treated with placebo, with an average reduction of 0.7 puffs (95% CI=-1.3 to -0.1) per day. In Study DB2113373, patients treated with INCRUSE ELLIPTA required less rescue salbutamol than those treated with placebo, with an average reduction of 0.3 puffs per day, however the result was not statistically significant (95%CI = -0.8 puffs to 0.2 puffs) per day.
Exacerbations
In a randomised, double-blind, 52-week study (CTT116855) of 10,355 adult patients with COPD and a history of 1 or more moderate or severe exacerbations within the prior 12 months, treatment with fluticasone furoate/umeclidinium/vilanterol (FF/UMEC/VI 100/62.5/25 mcg) once daily as a single inhaler was compared with a currently approved ICS/LABA once daily as a single inhaler. The primary endpoint was annual rate of on-treatment moderate and severe exacerbations in subjects treated with FF/UMEC/VI compared with ICS/LABA. The mean annual rate of exacerbations was 0.91 and 1.07 for FF/UMEC/VI and ICS/LABA, respectively.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: Pharmacological and toxicological effects seen with umeclidinium in nonclinical studies were those typically associated with either muscarinic antagonists and/or local irritancy. Umeclidinium (UMEC) has undergone a comprehensive toxicological evaluation. In the majority of studies, umeclidinium was administered by the inhaled route which resulted in systemic exposure.
In repeat dose inhalation toxicity studies with umeclidinium, the principal treatment-related findings of relevance to risk assessment were irritant effects in the respiratory tract and expected pharmacology-related cardiovascular effects. In patients following repeated inhaled doses of 62.5 mcg/day plasma concentrations of umeclidinium were typically lower than those achieved in animal toxicology studies (see 10.3 Pharmacokinetics).
Carcinogenicity: There was no evidence of treatment-related increases in tumour incidence in two year inhalation studies in rats and mice.
Genotoxicity: There was no evidence of genotoxicity in in vitro assays (Ames test and Mouse Lymphoma assay) or in the in vivo micronucleus test in rats.
Reproductive and Developmental Toxicity: Umeclidinium was not teratogenic in rats or rabbits. In a pre- and post-natal study, subcutaneous administration of umeclidinium to rats resulted in lower maternal body weight gain and food consumption and slightly decreased pre-weaning pup body weights in dams given 180 micrograms/kg/day dose (at exposures approximately 52X those achieved in subjects with COPD given 62.5 mcg/day umeclidinium based on AUC). In rabbits, the NOAEL following subcutaneous administration was 197X, and 35X following inhaled administration.
Local Tolerance: No or negligible hemolysis was evident in rat, dog and human blood treated with umeclidinium.
Umeclidinium was considered to be a non-sensitiser.
Umeclidinium was considered to be a mild/moderate dermal irritant using a reconstituted human skin model.
Umeclidinium was considered to be a mild/moderate ocular irritant using a reconstituted human epidermal model.
17 SUPPORTING PRODUCT MONOGRAPHS
ANORO ELLIPTA (Dry powder for oral inhalation, 62.5/25 mcg umeclidinium (as bromide)/vilanterol (as trifenatate)), Control No. 204866, Product Monograph, GlaxoSmithKline Inc. (August 9, 2017)
BREO ELLIPTA (Dry powder for oral inhalation, 100/25 mcg and 200/25 mcg fluticasone furoate/vilanterol (as trifenatate)), Control No. 213290, Product Monograph, GlaxoSmithKline Inc. (January 7, 2019)
TRELEGY ELLIPTA (Dry powder for oral inhalation, 100/62.5/25 mcg and 200/62.5/25 mcg fluticasone furoate/umeclidinium (as bromide)/vilanterol (as trifenatate)), Control No. 255950, Product Monograph, GlaxoSmithKline Inc. (January 17, 2022)