


Product Monograph - AA-Ipravent
RECENT MAJOR LABEL CHANGES
| 1 INDICATIONS, 1.2 Geriatrics | 09/2023 |
|---|---|
| 3 SERIOUS WARNINGS AND PRECAUTIONS | 09/2023 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 09/2023 |
| 7 WARNINGS AND PRECAUTIONS, General | 09/2023 |
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 09/2023 |
| 7 WARNINGS AND PRECAUTIONS, Fertility | 09/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics | 09/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics ................................................................................................................... 4
1.2 Geriatrics ................................................................................................................... 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations .............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration .......................................................................................................... 5
4.5 Missed Dose .............................................................................................................. 5
5 OVERDOSAGE ............................................................................................................. 6
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 6
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations ................................................................................................... 9
7.1.1 Pregnant Women .................................................................................................. 9
7.1.2 Breast-feeding ....................................................................................................... 9
7.1.3 Pediatrics ............................................................................................................... 9
7.1.4 Geriatrics ............................................................................................................. 10
8 ADVERSE REACTIONS................................................................................................ 10
8.1 Adverse Reaction Overview .................................................................................... 10
8.2 Clinical Trial Adverse Reactions .............................................................................. 10
8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 14
8.5 Post-Market Adverse Reactions .............................................................................. 14
9 DRUG INTERACTIONS ............................................................................................... 15
9.4 Drug-Drug Interactions ........................................................................................... 15
9.5 Drug-Food Interactions ........................................................................................... 15
9.6 Drug-Herb Interactions ........................................................................................... 15
9.7 Drug-Laboratory Test Interactions.......................................................................... 15
10 CLINICAL PHARMACOLOGY ....................................................................................... 16
10.1 Mechanism of Action .............................................................................................. 16
10.2 Pharmacodynamics ................................................................................................. 16
10.3 Pharmacokinetics .................................................................................................... 18
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 20
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 20
PART II: SCIENTIFIC INFORMATION ...................................................................................... 22
13 PHARMACEUTICAL INFORMATION ........................................................................... 22
14 CLINICAL TRIALS ....................................................................................................... 22
14.1 Clinical Trials by Indication ..................................................................................... 22
15 MICROBIOLOGY ....................................................................................................... 23
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 23
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 24
PATIENT MEDICATION INFORMATION ................................................................................. 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
AA-IPRAVENT (ipratropium bromide inhalation solution) is indicated for:
- the treatment of bronchospasm associated with acute exacerbations of chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema.
- the treatment of bronchospasm associated with acute severe exacerbations of bronchial asthma when used in conjunction with a beta2 adrenergic agonist such as salbutamol.
AA-IPRAVENT inhalation solution must be administered by means of nebulizer using gas flow (oxygen or compressed air).
1.1 Pediatrics
Pediatrics (<5 years of age): Based on the data reviewed by Health Canada, the efficacy and safety of AA-IPRAVENT in children younger than 5 years have not been established.
1.2 Geriatrics
Geriatrics (≥65 years of age): Elderly patients can use AA-IPRAVENT at the recommended dose.
2 CONTRAINDICATIONS
AA-IPRAVENT is contraindicated in:
- Patients with a history of hypersensitivity to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container or to atropine or its derivatives. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Counselling by healthcare professionals on smoking cessation should be the first step in treating patients with chronic obstructive pulmonary disease (COPD), who smoke, independent of the clinical presentation i.e., chronic bronchitis (with or without airflow limitation) or emphysema. Cessation of smoking produces dramatic symptomatic benefits and has been shown to confer a survival advantage.
4.2 Recommended Dose and Dosage Adjustment
- In adults, the average single dose of AA-IPRAVENT (ipratropium bromide) solution is 250 to 500 mcg of ipratropium bromide. In children, aged 5 to 12 years, the recommended dose is 125 to 250 mcg of ipratropium bromide. In most cases, dilution of the dose with sterile preservative-free saline is not necessary. However, volumes of AA-IPRAVENT solution less than 2 mL are not appropriate for nebulization and must be diluted with saline or another suitable nebulizer solution to make up a total fill volume of 2 to 5 mL. See 13 PHARMACEUTICAL INFORMATION.
- Treatment with AA-IPRAVENT solution may be repeated every 4 to 6 hours as necessary.
- Daily doses exceeding 2 mg in adults should be given under medical supervision.
- For the maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease, the recommended dose is 500 mcg of AA-IPRAVENT (ipratropium bromide) inhalation solution given 3 to 4 times per day.
- If therapy does not produce a significant improvement or if the patient’s condition gets worse, medical advice must be sought in order to determine a new plan of treatment. The patient should be instructed that in the case of acute or rapidly worsening dyspnea a healthcare professional should be consulted immediately.
4.4 Administration
Ipratropium bromide inhalation solution is intended only for inhalation with suitable nebulizing devices and must not be taken orally or administered parenterally.
It is recommended that the nebulized ipratropium bromide solution be administered via a mouth piece. If this is not available and a nebulizer mask is used, it must fit properly.
Nebulization should take place using a gas flow (oxygen or compressed air) of 6 to 10 L/minute and the solution nebulized to dryness over a 10 to 15 minute period.
4.5 Missed Dose
If a dose is missed, the next scheduled dose should be taken. An extra dose must not be taken.
5 OVERDOSAGE
Doses of ipratropium bromide up to 1.2 mg (60 puffs) have been administered by nebulization without the appearance of serious systemic anticholinergic effects. Minor systemic manifestations of anticholinergic action, including dry mouth, visual accommodation disturbances and increase of heart rate may occur.
Should signs of serious anticholinergic toxicity appear, cholinesterase inhibitors may be considered.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
Description
20 mL Bottle: AA-IPRAVENT solution is provided as 20 mL of clear, colourless or almost colourless solution containing 250 mcg/mL (0.025% w/v) ipratropium bromide in isotonic solution. This solution is preserved with benzalkonium chloride 250 mcg/mL (0.025% w/v) and EDTA-disodium 500 mcg/mL (0.05% w/v) at a pH of 3.4, and is presented in an amber glass bottle with screwcap.
7 WARNINGS AND PRECAUTIONS
See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Patients should be instructed in the proper use of the nebulizer.
Caution is advised against accidental release of the solution into the eyes.
In patients with glaucoma, prostatic hyperplasia, urinary retention and bladder neck obstruction, ipratropium bromide inhalation solution should be used with caution.
AA-IPRAVENT is a bronchodilator for the maintenance treatment of bronchospasm associated with COPD and since the drug has a slower onset of action than that of an adrenergic β2 agonist
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Inhalation | Solution 20 mL bottle (0.025%) | Benzalkonium chloride , edetate disodium dihydrate, hydrochloric acid, purified water and sodium chloride |
aerosol, it is not indicated for the initial treatment of acute episodes of bronchospasm where rescue therapy is required for rapid response.
If a reduced response to ipratropium bromide inhalation solution becomes apparent, the patient should seek medical advice.
Ipratropium bromide inhalation solution, when administered to patients with acute severe asthma, should be used with concomitant beta2 adrenergic agonist therapy. When used in combination with a beta2 adrenergic agonist, there is a potential for additional adverse effects and drug interactions (see PATIENT MEDICATION INFORMATION; see also the Product Monograph for Combivent® UDV for relevant information).
Excessive Use and Use with other Muscarinic Antagonists:
AA-IPRAVENT should not be used more frequently or at higher doses than recommended.
AA-IPRAVENT should not be administered concomitantly with other medications that contain a short- or long-acting muscarinic antagonist (e.g. ipratropium, tiotropium, glycopyrronium, aclidinium, umeclidinium).
Anticholinergic Effects:
Like other anticholinergic drugs, ipratropium bromide inhalation solution should be used with caution in patients with narrow-angle glaucoma or urinary retention.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity and 16 NON-CLINICLAL TOXICOLOGY, Genotoxicity.
Cardiovascular
Cardiovascular effects, such as cardiac arrhythmias (e.g. atrial fibrillation and tachycardia), may be seen after the administration of muscarinic receptor antagonists. See 8.3 Less Common Clinical Trial Adverse Reactions.
Driving and Operating Machinery
Patients should be advised that they may experience undesirable effects such as dizziness, accommodation disorder, mydriasis and blurred vision during treatment with ipratropium bromide inhalation solution. Caution should be exercised by the patient when driving or operating a vehicle or potentially dangerous machinery.
Gastrointestinal
Patients with cystic fibrosis may be more prone to gastrointestinal motility disturbances.
Immune
Hypersensitivity reactions including urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema may occur after administration of ipratropium bromide. In clinical trials and post-marketing experience with ipratropium containing products, hypersensitivity reactions such as skin rash, pruritus, angioedema of tongue, lips and face, urticaria (including giant urticaria), laryngospasm and anaphylactic reactions have been reported. See 8.5 Post-Market Adverse Reactions, Immune system disorders. If such a reaction occurs, therapy with ipratropium bromide inhalation solution should be stopped at once and alternative treatment should be considered. See 2 CONTRAINDICATIONS.
Ophthalmologic
Worsening of Narrow-Angle Glaucoma:
Ipratropium bromide inhalation solution should be used with caution in patients with narrow-angle glaucoma.
Care should be taken to ensure that the nebulizer mask fits the patient's face properly and that nebulized solution has not come in contact with the eyes. Patients should be advised that this may result in precipitation or worsening of narrow-angle glaucoma. There have been isolated cases of ocular complications (i.e., mydriasis, increased intraocular pressure, narrow angle closure glaucoma, eye pain) when nebulized ipratropium bromide either alone or in combination with an adrenergic beta2-agonist solution has come in contact with the eyes.
In patients with glaucoma or narrow anterior chambers, the administration by nebulizer of a combined ipratropium/beta2-agonist solution should be avoided unless measures (e.g., use of swimming goggles or use of a nebulizer with a mouthpiece) are taken to ensure that nebulized solution does not reach the eye. Prescribers and patients should be alert for signs and symptoms of acute narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a healthcare professional immediately should any of these signs or symptoms develop. Miotic drops alone are not considered to be effective treatment.
Renal
Worsening of Urinary Retention:
Ipratropium bromide inhalation solution should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of prostatic hyperplasia or bladder-neck obstruction (e.g., difficulty passing urine, painful urination). Instruct patients to consult a healthcare professional immediately should any of these signs or symptoms develop.
Reproductive Health: Female and Male Potential
Fertility
Clinical data on fertility are not available for ipratropium bromide. Nonclinical studies performed with ipratropium bromide showed no adverse effect on fertility. See 16 NON-
CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology.
Teratogenic Risk
Nonclinical studies have shown no embryotoxic or teratogenic effects following inhalation or intranasal application at doses considerably higher than those recommended in man.
Respiratory
Ipratropium bromide inhalation solution in the 20 mL multidose bottle contains preservatives (benzalkonium chloride and disodium ethylenediamine tetraacetic acid- EDTA-disodium). It has been reported that these preservatives may cause bronchoconstriction in some patients with hyper reactive airways.
Ipratropium bromide inhalation solution should not be used alone for the abatement of an acute asthmatic attack since the drug has a slower onset of effect than that of an adrenergic beta2-agonist.
Dyspnea:
The patient should be instructed to consult a healthcare professional immediately in the event of acute, rapidly worsening dyspnea. In addition, the patient should be warned to seek medical advice should a reduced response become apparent.
7.1 Special Populations
7.1.1 Pregnant Women
The safety of ipratropium bromide inhalation solution in pregnancy has not been established. There are no adequate and well-controlled studies of ipratropium bromide inhalation solution in pregnant women.
Because animal reproduction studies are not always predictive of human response, ipratropium bromide inhalation solution should be used during pregnancy only if the potential benefit justifies the potential risk to the unborn child.
7.1.2 Breast-feeding
No specific studies have been conducted on the excretion of ipratropium bromide in breast milk. It is considered unlikely that ipratropium bromide would reach the infant to an important extent, especially when administered by inhalation. However, caution should be exercised when ipratropium bromide inhalation solution is administered to nursing mothers. The benefits of ipratropium bromide inhalation solution use during lactation should therefore be weighed against possible effects on the infant.
7.1.3 Pediatrics
Pediatrics (<5 years of age): The efficacy and safety of ipratropium bromide in children younger than 5 years have not been established.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Elderly patients can use AA-IPRAVENT at the recommended dose.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Use of ipratropium bromide may result in:
- Ocular effects. See 7 WARNINGS AND PRECAUTIONS, Ophthalmologic.
- Urinary retention. See 7 WARNINGS AND PRECAUTIONS, Renal.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials, therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Acute Administration
The frequency of adverse reactions recorded in 214 patients receiving ipratropium bromide inhalation solution was as follows:
Table 2
| Adverse Reaction | % of Patients |
Cardiac disorders Palpitations | 0.5 |
Eye disorders Burning eyes | 0.9 |
Gastrointestinal disorders Dry mouth or throat Bad taste Nausea | 9.3 5.1 0.9 |
Nervous system disorders Tremor Headache | 4.2 0.5 |
| Adverse Reaction | % of Patients |
Respiratory thoracic and mediastinal disorders Exacerbation of symptoms Cough | 4.2 0.9 |
Skin and subcutaneous tissue disorders Sweating | 0.9 |
The adverse reaction judged to be most severe was exacerbation of bronchospasm. This occurred in eight patients treated with ipratropium bromide inhalation solution alone, six of whom withdrew from the clinical studies.
Bronchospasm occurred in 3 patients with acute severe asthma who received ipratropium bromide inhalation solution alone. In two patients, this was reversed after therapy with a beta2- sympathomimetic solution. The third patient received no other therapy.
The following table compares the incidence of adverse reactions of the combination of ipratropium bromide and a beta2-agonist (either fenoterol or salbutamol) solution with that of the beta2- agonist alone.
Table 3
| Adverse Reaction | lpratropium Bromide+ Beta2-Agonist (% of 94 patients) | Beta2- Agonist (% of 96 patients) |
Cardiac disorders Palpitations | 2.1 | 1.0 |
Gastrointestinal disorders Dry mouth Bad taste Vomiting | 16.0 16.0 2.1 | 28.1 13.5 2.1 |
Nervous system disorders Tremor Headache Dizziness Numbness in leg | 31.9 1.1 0.0 0.0 | 26.0 2.1 1.0 1.0 |
Respiratory thoracic and mediastinal disorders Cough | 1.1 | 0.0 |
| Vascular disorders |
| Adverse Reaction | lpratropium Bromide+ Beta2-Agonist (% of 94 patients) | Beta2- Agonist (% of 96 patients) |
| Flushing | 1.1 | 0.0 |
Chronic Administration
The frequency of adverse reactions reported as possibly related to ipratropium bromide treatment in 219 COPD patients participating in long-term (12-week) controlled clinical trials was as follows:
Table 4
| Adverse Reaction | % of Patients |
Cardiac disorders Palpitation | 0.9 |
Eye disorders Eye pain | 0.9 |
Gastrointestinal disorders Dry mouth Nausea | 2.7 0.9 |
Nervous system disorders Headache Tremor | 1.8 0.9 |
Renal and urinary disorders Urinary retention | 1.4 |
Respiratory thoracic and mediastinal disorders Coughing Dyspnea | 1.8 1.8 |
Observed adverse events occurring in at least 1% of subjects include rhinitis (0.9%) and sputum increase (0.9%).
The following other adverse reactions were reported in one patient each: bronchospasm, tachycardia and urticaria.
In addition, the following adverse events were observed in one patient each: bronchitis, chest pain, depression, fatigue, flu-symptoms, hypoaesthesia, increased saliva, insomnia, nervousness, pain, paraesthesia, pharyngitis and somnolence.
The frequency of adverse reactions reported as possibly related to drug treatment in greater than 1% of COPD patients participating in long-term (12-week) controlled clinical trials that compared the efficacy and safety of ipratropium bromide + beta2-agonists (metaproterenol or salbutamol) versus the beta2-agonist alone, was as follows:
Table 5
| Adverse Effect | % of Patients | |
lpratropium Bromide + Beta2- Agonist (n = 208) | Beta2-Agonist (n = 417) | |
Eye disorders Abnormal vision | 0.5 | 1.2 |
Gastrointestinal disorders Dry mouth Taste perversion Nausea Constipation Dyspepsia | 2.4 1.9 1.0 1.4 1.0 | 1.0 1.2 1.7 0.0 0.0 |
General disorders and administration site conditions Chest pain | 1.4 | 0.7 |
Nervous system disorders Headache Tremor Dizziness | 4.3 3.8 1.4 | 1.7 3.4 1.9 |
Psychiatric disorders Nervousness Insomnia | 3.8 1.9 | 1.9 0.2 |
Renal and urinary disorders Dysuria Micturition frequency | 1.0 1.0 | 0.2 0.2 |
Respiratory thoracic and mediastinal disorders Dyspnea Bronchitis Coughing Dysphonia | 2.4 2.9 1.4 1.0 | 3.4 2.9 1.0 0.2 |
| Adverse Effect | % of Patients | |
lpratropium Bromide + Beta2- Agonist (n = 208) | Beta2-Agonist (n = 417) | |
| Bronchospasm aggravated | 1.0 | 0.7 |
8.3 Less Common Clinical Trial Adverse Reactions
Less Common Clinical Trial Adverse Drug Reactions (<1%)
There have been isolated reports of ocular effects such as mydriasis, increased intraocular pressure, and acute glaucoma associated with the escape of nebulized ipratropium bromide, alone or in combination with a beta2-agonist solution into the eyes.
Side effects such as tachycardia and palpitations, supraventricular tachycardia and atrial fibrillation, ocular accommodation disturbances, nausea and urinary retention have been reversible, although the risk of urinary retention may be increased in patients with pre-existing outflow tract obstruction.
Ocular side effects have been reported. See 7 WARNING AND PRECAUTIONS, Ophthalmologic.
8.5 Post-Market Adverse Reactions
World-wide safety data, which includes post-marketing data, spontaneous reports and literature reports indicates that the most frequent non-respiratory side effects of ipratropium bromide inhalation solution are headache and dryness of mouth/throat.
The following are other post-marketing adverse reactions that have been reported for inhaled ipratropium bromide products.
Cardiac disorders: Palpitations, supraventricular tachycardia, atrial fibrillation, heart rate increased.
Eye disorders: Vision blurred, mydriasis, intraocular pressure increased, glaucoma, eye pain, halo vision, conjunctival hyperaemia, corneal oedema, accommodation disorder.
Gastrointestinal disorders: Nausea, gastrointestinal motility disorder, diarrhoea, constipation, vomiting, stomatitis, oedema mouth.
Immune system disorders: Immediate hypersensitivity reactions may occur after administration of ipratropium bromide inhalation solution. Allergic type reactions such as skin rash, pruritus, angioedema of the tongue, lips and face, urticaria (including giant urticaria), laryngospasm, oropharyngeal edema, bronchospasm, and anaphylactic reactions, may occur.
Nervous system disorders: Dizziness has been reported.
Renal and urinary disorders: Urinary retention.
Respiratory, thoracic and mediastinal disorders: Throat irritation, cough, bronchospasm paradoxical.
Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
9 DRUG INTERACTIONS
| It is strongly recommended not to mix ipratropium bromide inhalation solution with other drugs in the same nebulizer. |
|---|
9.4 Drug-Drug Interactions
The chronic co-administration of ipratropium bromide inhalation solution with other anticholinergic drugs has not been studied. There is potential for an additive interaction with concomitantly used anticholinergic medications. Therefore, AA-IPRAVENT should not be administered concomitantly with other medications that contain a short- or long-acting muscarinic antagonist (e.g. ipratropium, tiotropium, glycopyrronium, aclidinium, umeclidinium).
Ipratropium bromide inhalation solution with preservatives (i.e., from the 20 mL multidose bottle) should not be mixed with sodium cromoglycate, as this produces a cloudy solution caused by complexation between the preservatives and sodium cromoglycate.
In acute and maintenance therapy of chronic reversible airways obstruction, ipratropium bromide has been shown to provide additive bronchodilating effects to theophylline and beta-adrenoceptor agonists (sympathomimetic amines). Repeated inhalation of ipratropium bromide has not been linked to tolerance towards bronchodilating effects.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
lpratropium bromide is a quaternary ammonium compound with anticholinergic (parasympatholytic) properties. In nonclinical studies, it appears to inhibit vagally mediated reflexes by antagonizing the action of acetylcholine, the transmitter agent released from the vagus nerve. Anticholinergics prevent the increase in intracellular concentration of Ca++ which is caused by interaction of acetylcholine with the muscarinic receptor on bronchial smooth muscle. Ca++ release is mediated by the second messenger system consisting of IP3 (inositol triphosphate) and DAG (diacylglycerol).
The bronchodilation following inhalation of ipratropium bromide is primarily local and site specific to the lung and not systemic in nature.
On inhalation, the onset of action is noted within 5 to 15 minutes, with a peak response between 1 and 2 hours, lasting about 2 additional hours, with subsequent decline from the peak. Bronchodilation is still evident 8 hours after inhalation.
10.2 Pharmacodynamics
Large, single inhaled doses of ipratropium bromide have been given to man without any signs of toxicity. After the administration of 400 mcg to 10 healthy subjects, no changes were detected in pulse rate, blood pressure, intraocular pressure, salivary secretion, visual accommodation or electrocardiograms. Likewise, in a similar study no change in pulse rate or salivary secretion were seen when cumulative doses up to 1.2 mg were administered by inhalation to healthy volunteers.
Special studies utilizing normal therapeutic doses in asthmatic and chronic bronchitic patients have not revealed any systemic anticholinergic effects.
In one study, 14 patients were treated for 45 days with either ipratropium bromide 40 mcg q.i.d. or ipratropium bromide 40 mcg q.i.d. plus oral fenoterol 5 mg q.i.d. No changes in visual acuity, intraocular pressure, pupil size or accommodation of vision occurred. Micturition function studies in 20 male patients showed no differences in urinary flow, total flow time and time until maximum flow between placebo and ipratropium bromide 40 mcg t.i.d. administered for 3 days.
A wide variety of challenge studies have been conducted using ipratropium bromide as a protective agent. In pharmacologically induced bronchospasm, ipratropium bromide, in clinical doses, was very effective against methacholine and acetylcholine, moderately effective against propranolol but had no effect against histamine or serotonin. Studies in exercise induced bronchospasm have yielded variable results. Some investigations have indicated that ipratropium bromide has little or no effect but other studies have shown that some patients, at least, were protected against bronchospasm induced by exercise. Likewise, the protection against cold air induced bronchospasm has been variable.
Antigen challenge studies have demonstrated that ipratropium bromide offers some protection against the “early” allergic asthma response, but has no effect on the “late” response.
The Lung Health Study
The Lung Health Study was a randomized multi centre clinical trial carried out from October 1986 to April 1994 in North America. It was designed to test the effectiveness of intervention-smoking cessation and bronchodilator administration in smokers aged 35 to 60 years who have mild obstructive pulmonary disease. The main outcome or end point was the rate of change and cumulative change in FEV1 over a 5-year period.
A total of 5887 male and female smokers, aged 35 to 60 years, with spirometric signs of early chronic obstructive pulmonary disease were recruited. Participants were randomized to one of the following groups: (1) smoking intervention plus bronchodilator, (2) smoking intervention plus placebo, or (3) no intervention.
Smoking intervention consisted of an intensive 12-session smoking cessation program combining behaviour modification and use of nicotine gum, with continuing 5-year maintenance program to minimize relapse. Two puffs ipratropium bromide was prescribed three times daily from a metered-dose-inhaler.
The results showed that participants in the two smoking intervention groups showed significantly smaller declines in FEV1 than did those in the control group. Most of this difference occurred during the first year following entry into the study and was attributable to smoking cessation, with those who achieved sustained smoking cessation experiencing the largest benefit. The benefit associated with the use of the ipratropium bromide vanished after the ipratropium bromide was discontinued at the end of the study.
In summary, the results showed that smoking intervention reduced the rate of decline in FEV1 in middle aged smokers with mild airways obstruction who remained non-smokers throughout the 5 years. The other intervention, administration of ipratropium bromide, did not alter the rate of decline in lung function. There was a small one time improvement in lung function associated with the onset of ipratropium use, but this disappeared rapidly when ipratropium use was discontinued at the end of the study. Otherwise, the regular use of ipratropium bromide had no effect on the rate of decline of lung function over 5 years in patients studied.
Non-clinical pharmacology
lpratropium bromide is an anticholinergic agent which, when delivered by aerosol, exerts its effects primarily in the bronchial tree. It abolishes acetylcholine-induced bronchospasm in the guinea pig and dog after intravenous administration of ED50 of 0.15 and 0.40 mcg/kg with a transient effect on blood pressure. By inhalation, approximately 25 mcg of ipratropium bromide produces a 50% inhibition of acetylcholine-induced bronchospasm in the dog with no detectable effect on blood pressure but with an increased duration of action compared to i.v. administration. Histological evaluation of human bronchial mucosae following chronic inhalation of ipratropium bromide showed no alterations of epithelial, ciliated or goblet cells. Short term mucociliary clearance in normal and bronchitic subjects was not adversely affected by 200 mcg of inhaled ipratropium bromide.
The anticholinergic effects of ipratropium bromide were evaluated in several other organ systems following oral, subcutaneous, intravenous and inhalation administration. In dogs, a 50% increase in heart rate resulted from a s.c. dose of about 0.011 mg/kg, equipotent to atropine, but the equi-effective oral dose of ipratropium was 58 times greater. By inhalation, no increase in heart rate or pathological changes in ECG pattern were recorded at doses up to 8 mg. In another study, blood pressure and heart rate in the dog could be modulated after intravenous (i.v.) administration of low doses of ipratropium but metered aerosol administration of 100 puffs (40 mcg/puff) was required to produce an 11% increase in heart rate.
Salivary secretion in rat, mouse and dog was effectively inhibited by low parenteral doses of ipratropium bromide (0.001 to 0.032 mg/kg) but when given by the oral route, the effective dose increased over 100-fold. Aerosol administration in dogs of about 65 puffs (0.04 mg/puff) produced a 50% decrease in salivary flow. Similarly, effects on gastric secretion in the rat showed at least a 100-fold difference between effective enteral and subcutaneous doses.
Mydriatic effects of ipratropium bromide in mice were approximately equipotent to atropine after s.c. doses but were 10 to 20 times less after oral administration. Tests in the rabbit indicated that doses up to 100 mg/kg had no effect on the central nervous system.
lpratropium bromide administered s.c. inhibited the secretory effects of the cholinergic agonist, oxitropium, in mice. It also inhibited spasmolytic effects equivalent to or greater than atropine in isolated guinea pig gut. In vitro tests with isolated rectum of the guinea pig demonstrated the effectiveness of ipratropium bromide in suppressing the spasmogenic effects of acetylcholine and pilocarpine. It was ineffective against histamine or barium chloride induced spasm. lpratropium bromide exerted anticholinergic effects on the in situ bladder and intestine preparations of the dog. Intravenous doses were 500 times more potent than oral or intraduodenal administration.
10.3 Pharmacokinetics
Absorption
Ipratropium bromide is absorbed quickly after oral inhalation of a nominal dose of 40 mcg administered from a pressurized metered dose inhaler. The peak plasma concentration (mean Cmax = 32 pg/mL) is reached within 5 minutes after inhalation. The therapeutic effect of ipratropium bromide is produced by a local action in the airways. Therefore time courses of bronchodilation and systemic pharmacokinetics do not run in parallel. The plasma concentration-versus-time curve was similar to that seen after oral administration, likely reflecting the large fraction of inhaled dose which is deposited on the pharyngeal mucosa and swallowed.
Intravenous administration of 1.0 mg in man showed a rapid distribution into tissues (half-life of an alpha phase approximately five minutes), and a terminal half-life (beta phase) of 3 to 4 hours. Plasma concentrations after inhaled ipratropium bromide were about 1000 times lower than equipotent oral or intravenous doses (15 and 0.15 mg, respectively).
Cumulative renal excretion (0 to 24 hrs) of ipratropium (parent compound) is approximated to 46% of an intravenously administered dose, below 1% of an oral dose and approximately 3 to 13% of an inhaled dose. Based on these data, the apparent systemic bioavailability of oral and inhaled doses of ipratropium bromide is estimated at 2% and 7 to 28%, respectively. Taking this into account, swallowed dose portions of ipratropium bromide do not relevantly contribute to systemic exposure.
Distribution
Kinetic parameters describing the disposition of ipratropium were calculated from plasma concentrations after i.v. administration. A rapid biphasic decline in plasma concentrations is observed. The apparent volume of distribution at steady-state (Vdss) is approximately 176 L (≈ 2.4 L/kg).
The drug is minimally (less than 20%) bound to plasma proteins. Nonclinical data indicate that the quaternary amine ipratropium does not cross the placental or the blood-brain barrier.
Metabolism
The half-life of the terminal elimination phase is approximately 1.6 hours. Ipratropium has a total clearance of 2.3 L/min and a renal clearance of 0.9 L/min. After intravenous administration approximately 60% of a dose is metabolised, the major portion probably in the liver by oxidation.
Elimination
Up to 8 metabolites of ipratropium bromide have been detected in man, dog and rat. In an excretion balance study cumulative renal excretion (6 days) of drug-related radioactivity (including parent compound and all metabolites) accounted for 72.1% after intravenous administration, 9.3% after oral administration and 3.2% after inhalation. Total radioactivity excreted via the faeces was 6.3% following intravenous application, 88.5% following oral dosing and 69.4% after inhalation. Regarding the excretion of drug-related radioactivity after intravenous administration, the main excretion occurs via the kidneys. The half-life for elimination of drug-related radioactivity (parent compound and metabolites) is 3.6 hours. The main urinary metabolites bind poorly to the muscarinic receptor and have to be regarded as ineffective.
Thirty-nine percent of the active ingredient is excreted renally after intravenous administration, 4.4% to 13.1% after inhalation from a metered dose inhaler is excreted as unchanged compound in urine.
Special Populations and Conditions
- Pediatrics: The efficacy and safety of ipratropium bromide in children younger than 5 years have not been established.
11 STORAGE, STABILITY AND DISPOSAL
Unopened bottles of AA-IPRAVENT solution should be stored at controlled room temperature (between 15°C and 30°C). Solutions diluted with preservative free sterile Sodium Chloride Inhalation Solution, USP 0.9% should be used within 24 hours from time of dilution when stored at room temperature and within 48 hours when stored in the refrigerator.
A controlled Preservative Challenge test, done in accordance with the current USP guideline for Preservative Efficacy Testing, indicated that bottles of ipratropium bromide inhalation solution, opened and closed several times, simulating patient use, were stable for up to 28 days when stored at room temperature (15° - 30°C).
Controlled laboratory experiments using mixtures of ipratropium bromide solution with Alupent® (orciprenaline sulfate), Berotec® (fenoterol hydrobromide) or salbutamol sulfate (6 mg/mL preserved with benzalkonium chloride) solutions and diluted with a sterile bacteriostatic sodium chloride solution 0.9% (i.e., normal saline), preserved with benzalkonium chloride, indicated that such mixtures were stable for 7 days at room temperature. For the preparation of such mixtures, it is recommended that only sterile solutions of bacteriostatic sodium chloride 0.9% preserved with 0.01% benzalkonium chloride be used to maintain the level of preservative in the mixture.
The safety of preservatives other than benzalkonium chloride has not been established.
Medicines should not be disposed of down the drain or in household garbage. Any unused product or waste material should be disposed of in accordance with local requirements.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Incompatibilities:
AA-IPRAVENT solution with preservatives (i.e., from the 20 mL multidose bottle) should not be mixed with sodium cromoglycate solution, as this produces a cloudy solution caused by complexation between the preservatives and sodium cromoglycate.
The solution is physically compatible with Alupent® (orciprenaline sulfate), Berotec® (fenoterol hydrobromide) or salbutamol sulfate (6 mg/mL) solutions. If such mixtures are prepared, they should be diluted with preservative free sterile sodium chloride solution 0.9% and used immediately. Any unused portion of such combined solutions must be discarded.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: ipratropium bromide monohydrate.
Chemical name: (8r)-3α-hydroxy-8-isopropyl-1αH, 5αH-tropanium bromide (±)-tropate monohydrate.
Molecular formula and molecular mass C20H30NO3Br•H2O; 430.4 g/mol
Structural formula:
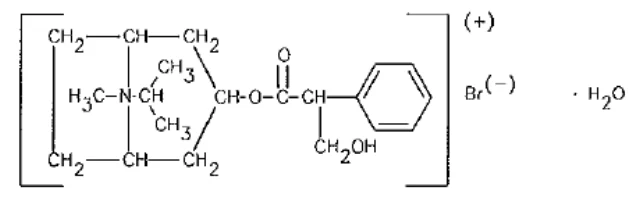
Physicochemical properties: White crystalline substance with a bitter taste. Freely soluble in water and alcohol; insoluble in chloroform and ether. In neutral and acid solutions the substance is rather stable; in alkaline solutions the ester bond is rapidly hydrolyzed. The melting point is 229 - 231°C with decomposition. [α]20=0° D
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
In controlled 12-week studies in patients with bronchospasm associated with chronic obstructive pulmonary disease (chronic bronchitis and emphysema), significant improvements in pulmonary function (FEV1 and FEF25-75% in increases of 15% or more) occurred within 15 minutes, reached a peak in 1 to 2 hours, and persisted for periods of 4 to 5 hours in the majority of patients, with 25 to 38% of the patients demonstrating increases of at least 15% at 7 to 8 hours. Continued effectiveness of ipratropium bromide inhalation solution was demonstrated throughout the 12-week period. In addition, significant changes in forced vital capacity (FVC) have been demonstrated.
Additional controlled 12-week studies were conducted to evaluate the safety and efficacy of ipratropium bromide inhalation solution administered concomitantly with bronchodilator solutions of orciprenaline or salbutamol, compared with the administration of each of the beta agonists alone.
Combined therapy produced significant additional responses in FEV1, FVC and FEF25-75%. On combined therapy, the median duration of 15% improvement in FEV1 was 5 to 7 hours, compared with 3 to 4 hours in patients receiving a beta agonist alone.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Toxicological effects seen with ipratropium bromide in single dose and multiple dose studies conducted in rodents and non-rodent species were typical of those associated with high doses of muscarinic receptor antagonists (e.g. mydriasis; dryness of oral, nasal, and optic mucosa; lethargy; emesis; increased heart rate).
Carcinogenicity
Ipratropium bromide was tested individually for neoplastic properties in several carcinogenicity studies. Carcinogenicity studies in mice (107 weeks duration) and rats (114 weeks duration) utilizing oral doses of up to 6 mg/kg were performed. Ipratropium bromide revealed no carcinogenic potential when tested orally in mice and rats.
Genotoxicity
Ipratropium bromide was tested in numerous in-vivo and in-vitro genotoxicity tests and showed no evidence of mutagenic properties.
Three Ames tests, a micronucleus test in mice, a cytogenetic study in Chinese hamsters, and a dominant lethal test in mice were performed to assess the mutagenic potential of ipratropium bromide. Two positive tests (one Ames and the micronucleus study) were apparently spurious as they could not be reproduced with subsequent exhaustive experimentation. In the cytogenetic study, a dose-related increase in the number of chromatid gaps, but not of other aberrations, was seen. The significance of this finding is not known. All other test results were negative.
Reproductive and Developmental Toxicology
Three teratology studies, one in mice using oral doses of 2 and 10 mg/kg and two in rats have been conducted. The first rat study used the same dosages while the second employed 10 and 20 mg/kg. None of these studies revealed any drug induced fetal abnormalities.
A similar oral study in rabbits utilizing doses of 2 and 10 mg/kg again demonstrated no teratogenic or embryotoxic effects of ipratropium bromide.
An inhalation teratology study in rabbits using doses of 0.3, 0.9 and 1.8 mg/kg demonstrated no effect on litter parameters and no embryotoxic or teratogenic effects.
A fertility study in rats with oral doses of 5, 10 and 500 mg/kg given 60 days prior to and during early gestation was performed. Fertility was delayed in eight of 20 couples at 500 mg/kg dose and spurious pregnancy in five of 20 females occurred at this dose. In addition, the conception rate was decreased in 75% of females at this dose. No embryotoxic or teratogenic effects were observed.
Apart from these findings, the studies performed with ipratropium bromide revealed only marginal effects, if any, on embryos, foetuses and pups and these only in the range of maternal toxicity. Ipratropium bromide did not affect fertility of male or female rats at oral doses up to 50 mg/kg (approximately 3,400 times the MRHDD on a mg/m2 basis).
17 SUPPORTING PRODUCT MONOGRAPHS
1 Atrovent® (lpratropium Bromide Inhalation Solution), submission control 104456, Product Monograph, Boehringer lngelheim (Canada) Ltd., (MAY 16, 2006).
2 Atrovent® HFA (lpratropium Bromide Pressurized Inhalation Solution), submission control 230291, Product Monograph, Boehringer lngelheim (Canada) Ltd., (NOV 04, 2019).
3 Combivent® UDV [lpratropium Bromide (as Monohydrate) and Salbutamol (as Salbutamol Sulfate) Nebulizer Solution], submission control 186512, Product Monograph, Boehringer lngelheim (Canada) Ltd., (NOV 25, 2015).