


Product Monograph - Apo-Methylphenidate ER
RECENT MAJOR LABEL CHANGES
| 4 DOSAGE AND ADMINISTRATION, 4.5 Missed Dose | 07/2023 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Neurologic, Serotonin toxicity/Serotonin syndrome | 07/2023 |
| 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential | 07/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES..............................................................................................2
TABLE OF CONTENTS ................................................................................................................2
PART I: HEALTH PROFESSIONAL INFORMATION .......................................................................4
1 INDICATIONS ................................................................................................................4
1.1 Pediatrics .............................................................................................................4
1.2 Geriatrics .............................................................................................................5
2 CONTRAINDICATIONS ...................................................................................................5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ..............................................................5
4 DOSAGE AND ADMINISTRATION ...................................................................................5
4.1 Dosing Considerations ..........................................................................................5
4.2 Recommended Dose and Dosage Adjustment .......................................................6
4.4 Administration .....................................................................................................8
4.5 Missed Dose .........................................................................................................8
5 OVERDOSAGE ...............................................................................................................8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ...................................9
7 WARNINGS AND PRECAUTIONS ....................................................................................9
7.1 Special Populations............................................................................................. 16
7.1.1 Pregnant Women ............................................................................................... 16
7.1.2 Breast-feeding .................................................................................................... 16
7.1.3 Pediatrics ........................................................................................................... 16
7.1.4 Geriatrics ........................................................................................................... 16
8 ADVERSE REACTIONS .................................................................................................. 17
8.1 Adverse Reactions Overview ............................................................................... 17
8.2 Clinical Trial Adverse Reactions ........................................................................... 18
8.2.1 Clinical Trial Adverse Reactions – Pediatrics......................................................... 23
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 25
8.5 Post-Market Adverse Reactions .......................................................................... 25
9 DRUG INTERACTIONS .................................................................................................. 28
9.1 Serious Drug Interactions.................................................................................... 28
9.2 Drug Interactions Overview ................................................................................ 28
9.3 Drug-Behavioural Interactions ............................................................................ 28
9.4 Drug-Drug Interactions ....................................................................................... 28
9.5 Drug-Food Interactions ....................................................................................... 29
9.6 Drug-Herb Interactions ....................................................................................... 29
9.7 Drug-Laboratory Test Interactions....................................................................... 29
10 CLINICAL PHARMACOLOGY ......................................................................................... 30
10.1 Mechanism of Action .......................................................................................... 30
10.2 Pharmacodynamics ............................................................................................ 30
10.3 Pharmacokinetics ............................................................................................... 30
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 35
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 36
PART II: SCIENTIFIC INFORMATION ........................................................................................ 37
13 PHARMACEUTICAL INFORMATION .............................................................................. 37
14 CLINICAL TRIALS .......................................................................................................... 37
14.1 Clinical Trials by Indications ................................................................................ 37
Attention Deficit Hyperactivity Disorder in Children...................................................... 38
Attention Deficit Hyperactivity Disorder in Adolescents ................................................ 40
Attention Deficit Hyperactivity Disorder in Adults......................................................... 41
14.2 Comparative Bioavailability Studies..................................................................... 42
15 MICROBIOLOGY .......................................................................................................... 45
16 NON-CLINICAL TOXICOLOGY ....................................................................................... 45
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 48
PATIENT MEDICATION INFORMATION ................................................................................... 49
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-METHYLPHENIDATE ER (methylphenidate hydrochloride extended-release tablets) is indicated for:
the treatment of Attention Deficit Hyperactivity Disorder (ADHD) in:
- Children (6 to 12 years of age)
- Adolescents (13 to 18 years of age)
- Adults (> 18 years of age)
Need for Comprehensive Treatment Program
APO-METHYLPHENIDATE ER is indicated as an integral part of a total treatment program for ADHD that may include other measures (psychological, educational, social) for patients with this syndrome. Drug treatment may not be indicated for all patients with this syndrome. Drug treatment is not intended for use in the patient who exhibits symptoms secondary to environmental factors and/or other primary psychiatric disorders, including psychosis. Appropriate educational placement is essential in children and adolescents with this diagnosis and psychosocial intervention is often helpful. When remedial measures alone are insufficient, the decision to prescribe drug treatment medication will depend upon the physician’s assessment of the chronicity and severity of the patient’s symptoms.
Long-Term Use
The effectiveness of methylphenidate hydrochloride extended-release tablets for long-term use, i.e., for more than 4 weeks in children and adolescents or 7 weeks in adults, has not been systematically evaluated in placebo-controlled trials. Therefore, the physician who elects to use APO-METHYLPHENIDATE ER for extended periods should periodically re-evaluate the long-term usefulness of the drug for the individual patient (see 4.2 Recommended Dose and Dosage Adjustment, Maintenance/Extended Treatment).
1.1 Pediatrics
Pediatrics (6 to 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of methylphenidate hydrochloride extended-release tablets in pediatric patients from 6 to 18 years of age has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 14 CLINICAL TRIALS).
Pediatrics (< 6 years of age): APO-METHYLPHENIDATE ER should not be used in children under six years of age. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for children under six years of age.
1.2 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
2 CONTRAINDICATIONS
APO-METHYLPHENIDATE ER is contraindicated in:
- Patients who are hypersensitive to methylphenidate or to any ingredient in the formulation or component of the container. For a complete listing, see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the Product Monograph.
- Thyrotoxicosis
- Advanced arteriosclerosis
- Symptomatic cardiovascular disease
- Moderate to severe hypertension (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular)
- Glaucoma (see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic)
- During treatment with monoamine oxidase inhibitors, and also within a minimum of 14 days following discontinuation of a monoamine oxidase inhibitor (hypertensive crises may result) (see 9.1 Serious Drug Interactions and 9.4 Drug-Drug Interactions).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
APO-METHYLPHENIDATE ER should be administered starting at the lowest possible dose. Dosage should then be individually and slowly adjusted, to the lowest effective dosage, since individual patient response to APO-METHYLPHENIDATE ER varies widely.
APO-METHYLPHENIDATE ER should not be used in patients with symptomatic cardiovascular disease and should generally not be used in patients with known structural cardiac abnormalities (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
Children: Theoretically there exists a pharmacological potential for all ADHD drugs to increase the risk of sudden/cardiac death. Although confirmation of an incremental risk for sudden/cardiac death arising from treatment with ADHD medications is lacking, prescribers should consider this potential risk.
All drugs with sympathomimetic effects prescribed in the management of ADHD should be used with caution in patients who: a) are involved in strenuous exercise or activities, b) use other sympathomimetic ADHD drugs or c) have a family history of sudden/cardiac death. Prior to the initiation of treatment with sympathomimetic medications, a personal and family history (including assessment for a family history of sudden death or ventricular arrhythmia) and physical exam should be obtained to assess for the presence of cardiac disease. In patients with relevant risk factors and based on the clinician’s judgment, further cardiovascular evaluation may be considered (e.g., electrocardiogram and echocardiogram). Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during ADHD treatment should undergo a prompt cardiac evaluation. Patients who are considered to need extended treatment with APO-METHYLPHENIDATE ER should undergo periodic evaluation of their cardiovascular status (see 7 WARNINGS AND PRECAUTIONS).
4.2 Recommended Dose and Dosage Adjustment
General
APO-METHYLPHENIDATE ER should be administered orally once daily in the morning, with or without food. For patients new to methylphenidate, the starting dose for APO-METHYLPHENIDATE ER should be 18 mg daily. For patients currently on a methylphenidate-based product, see the conversion table below.
Dose Selection
Patients New to Methylphenidate
The recommended starting dose of APO-METHYLPHENIDATE ER for patients who are not currently taking methylphenidate, or for patients who are on stimulants other than methylphenidate, is 18 mg once daily for all age groups.
Table 1: Recommended Starting Dose and Maximum Dosage of APO-METHYLPHENIDATE ER for Patients New to Methylphenidate
| Patient Age | Recommended Starting Dose | Maximum Dosage |
| Children (6-12 years of age) | 18 mg/day | 54 mg/day |
| Adolescents (13-18 years of age) | 18 mg/day | 54 mg/day |
| Adults (>18 years of age) | 18 mg/day | 72 mg/day |
A limited number of adolescents have been treated with methylphenidate hydrochloride extended-release tablets 72 mg/day in the open- label extension of Study 4 (n=62). A limited number of adults have been treated with doses above the recommended maximum daily dose, up to 90 mg/day (n=41 in study 5).
Patients Currently Using Methylphenidate Hydrochloride
The recommended conversion dose of APO-METHYLPHENIDATE ER for patients who are currently taking methylphenidate hydrochloride b.i.d., t.i.d., or sustained-release (SR) at doses of 10 to 60 mg/day is provided in Table 2. Dosing recommendations are based on current dose regimen and clinical judgment.
Table 2: Recommended Dose Conversion from Methylphenidate Hydrochloride Regimens to APO-METHYLPHENIDATE ER
| Previous Methylphenidate Hydrochloride Daily Dose | Recommended APO-METHYLPHENIDATE ER Conversion Dose |
| 5 mg methylphenidate hydrochloride b.i.d./t.i.d. or 20 mg methylphenidate hydrochloride SR | 18 mg q. a.m. |
| 10 mg methylphenidate hydrochloride b.i.d./t.i.d.or 40 mg methylphenidate hydrochloride SR | 36 mg q. a.m. |
| 15 mg methylphenidate hydrochloride b.i.d./t.i.d. or 60 mg methylphenidate hydrochloride SR | 54 mg q. a.m. |
| 20 mg methylphenidate hydrochloride b.i.d./t.i.d | 72 mg q. a.m. |
A dosage strength of 27 mg is available for physicians who wish to prescribe between the 18 mg and 36 mg dosages.
Dose Titration
Dosage should be individualized according to the needs and responses of the patient. Based on an assessment of clinical benefit and tolerability, doses may be adjusted at weekly intervals for patients who have not achieved an optimal response.
Maintenance/Extended Treatment
There is no evidence available from controlled trials to indicate how long the patient with ADHD should be treated with methylphenidate hydrochloride extended-release tablets. It is generally agreed that pharmacological treatment of ADHD may be needed for extended periods. The physician who elects to use APO-METHYLPHENIDATE ER for extended periods in patients with ADHD should periodically re-evaluate the long-term usefulness of the drug for the individual patient with trials off medication to assess the patient’s functioning without pharmacotherapy.
Dose Reduction and Discontinuation
If paradoxical aggravation of symptoms or other adverse events occur, the dosage should be reduced or, if necessary, the drug should be discontinued.
If improvement is not observed after appropriate dosage adjustment over a one-month period, the drug should be discontinued.
4.4 Administration
APO-METHYLPHENIDATE ER tablets must be swallowed whole with liquids, and must not be chewed, divided or crushed. In dogs, the intravenous injection of the pulverized methylphenidate hydrochloride extended-release tablets resulted in death (see 16 NON-CLINICAL TOXICOLOGY, Acute Toxicity).
4.5 Missed Dose
If a dose of APO-METHYLPHENIDATE ER is missed, the patient should be instructed to take the next dose in the usual amount at the usual time the next morning. Patients should be instructed not to take an afternoon dose and not to double the dose.
5 OVERDOSAGE
Signs and Symptoms
Signs and symptoms of APO-METHYLPHENIDATE ER overdosage, resulting principally from overstimulation of the CNS and from excessive sympathomimetic effects, may include the following: vomiting, agitation, muscle twitching, convulsion, grand mal convulsions, confusional state, hallucination (auditory and/or visual), hyperhidrosis, headache, pyrexia, tachycardia, palpitations, heart rate increased, sinus arrhythmia, hypertension, rhabdomyolysis, mydriasis and dry mouth.
Recommended Management of Overdosage
Treatment of APO-METHYLPHENIDATE ER overdosage consists of appropriate supportive measures. The patient must be protected against self-injury and against external stimuli that would aggravate the overstimulation already present. The efficacy of activated charcoal has not been established. Intensive care must be provided to maintain adequate circulation and respiratory exchange; external cooling procedures may be required for pyrexia.
Efficacy of peritoneal dialysis or extracorporeal hemodialysis for methylphenidate hydrochloride extended-release tablets overdosage has not been established. The prolonged release of methylphenidate from APO-METHYLPHENIDATE ER should be considered when treating patients with overdose. Alcohol may induce the production of ethylphenidate. The amount of ethylphenidate production is proportional to the blood alcohol concentration (see 9.2 Drug Interactions Overview). As with the management of all overdosage, the possibility of multiple drug ingestion, including alcohol, should be considered.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Extended-Release Tablet, 18 mg, 27 mg, 36 mg and 54 mg | Anhydrous lactose, hydroxypropyl cellulose, hydroxypropyl methylcellulose, iron oxide black (27 mg), iron oxide red (54 mg), iron oxide yellow (18 mg), magnesium stearate, polyethylene glycol, polyvinyl acetate phthalate and titanium dioxide. |
APO-METHYLPHENIDATE ER contain methylphenidate hydrochloride as the medicinal ingredient and are available in 18 mg, 27 mg, 36 mg and 54 mg dosage strengths.
The 18 mg capsule-shaped, film coated tablets are yellow and engraved “APO” on one side and “MPD18” on the other side. Available in bottles and unit-dose blisters of 100 tablets.
The 27 mg capsule-shaped, film coated tablets are light-gray and engraved “APO” on one side and “MPD27” on the other side. Available in bottles and unit-dose blisters of 100 tablets.
The 36 mg capsule-shaped, film coated tablets are white and engraved “APO” on one side and “MPD36” on the other side. Available in bottles and unit-dose blisters of 100 tablets.
The 54 mg capsule-shaped, film coated tablets are brownish-red and engraved “APO” on one side and “MPD54” on the other side. Available in bottles and unit-dose blisters of 100 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
APO-METHYLPHENIDATE ER is intended for oral use only. In dogs, the intravenous injection of the pulverized methylphenidate hydrochloride extended-release tablets resulted in death (see 16 NON-CLINICAL TOXICOLOGY, Acute Toxicity).
Fatigue
APO-METHYLPHENIDATE ER should not be used for the prevention or treatment of normal fatigue states.
Information for Patients
Patients should be informed that APO-METHYLPHENIDATE ER should be swallowed whole with the aid of liquids. Tablets should not be chewed, divided, or crushed. Patient information is provided in the PATIENT MEDICATION INFORMATION section. To assure safe and effective use of APO-METHYLPHENIDATE ER, the information and instructions provided in the PATIENT MEDICATION INFORMATION section should be discussed with patients.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY; Carcinogenicity, Genotoxicity and Reproductive and Developmental Toxicity for discussion on animal data.
Cardiovascular
Hypertension and Other Cardiovascular Conditions
APO-METHYLPHENIDATE ER is contraindicated in moderate to severe hypertension and should be used cautiously in patients with mild hypertension and other cardiovascular conditions. Blood pressure should be monitored at appropriate intervals in patients receiving
APO-METHYLPHENIDATE ER, especially in patients with hypertension.
In the laboratory classroom clinical trials in children (Studies 1 and 2), both methylphenidate hydrochloride extended-release tablets and methylphenidate t.i.d. increased resting pulse by an average of 2 to 6 beats per minute (bpm) and produced average increases of systolic blood pressure (SBP) and diastolic blood pressure (DBP) of approximately 1 to 4 mm Hg during the day, relative to placebo. In the double-blind, placebo-controlled study in adults (Study 5), changes in mean DBP and SBP were observed with methylphenidate hydrochloride extended-release tablets doses up to 72 mg. A statistically significant (p<0.05) mean increase in standing DBP and SBP versus baseline was reached at Week 1 in the 72 mg methylphenidate hydrochloride extended-release tablets dose group (mean increase of 2.0 mm Hg for standing DBP and 4.0 mm Hg for standing and supine SBP) but not at later time points. A statistically significant increase in pulse was observed for all methylphenidate hydrochloride extended-release tablets dose groups (18 mg, 36 mg and 72 mg) versus baseline (range of mean increase of 2.0 to 10.6 bpm). Therefore, caution is advised in treating patients whose underlying medical conditions might be compromised by increases in blood pressure or heart rate, e.g., those with pre-existing hypertension, heart failure or recent myocardial infarction.
Pre-Existing Cardiovascular and Cerebral Vascular Conditions
APO-METHYLPHENIDATE ER is contraindicated in advanced arteriosclerosis and symptomatic cardiovascular disease. CNS stimulants should be used with caution in patients with other pre-existing cardiovascular or cerebrovascular conditions, taking into account risk predictors for these conditions. Patients should be screened for pre-existing or underlying cardiovascular or cerebrovascular conditions before initiation of treatment with APO-METHYLPHENIDATE ER and monitored for new conditions of the heart or brain during the course of treatment.
Sudden Death and Pre-existing Structural Cardiac Abnormalities or Other Serious Heart Problems
- Children and Adolescents
Sudden death has been reported in association with stimulant drugs used for ADHD treatment at usual doses in children and adolescents with structural cardiac abnormalities or other serious cardiac problems. Although some serious heart problems alone carry an increased risk of sudden death, APO-METHYLPHENIDATE ER generally should not be used in children, adolescents, or adults with known structural cardiac abnormalities, cardiomyopathy, serious heart rhythm abnormalities, or other serious cardiac problems that may place them at increased vulnerability to the sympathomimetic effects of a stimulant drug.
- Adults
Sudden deaths, stroke, and myocardial infarction have been reported in adults taking stimulant drugs at usual doses for ADHD. Although the role of stimulants in these adult cases is also unknown, adults have a greater likelihood than children of having serious structural cardiac abnormalities, cardiomyopathy, serious heart rhythm abnormalities, coronary artery disease, or other serious cardiac problems. Adults with such abnormalities should also generally not be treated with stimulant drugs (see 2 CONTRAINDICATIONS).
- General
Theoretically there exists a pharmacological potential for all ADHD drugs to increase the risk of sudden/cardiac death. Although confirmation of an incremental risk for sudden/cardiac death arising from treatment with ADHD medications is lacking, prescribers should consider this potential risk.
All drugs with sympathomimetic effects prescribed in the management of ADHD should be used with caution in patients who: a) are involved in strenuous exercise or activities, b) use other sympathomimetic ADHD drugs or c) have a family history of sudden/cardiac death. Prior to the initiation of treatment with sympathomimetic medications, a personal and family history (including assessment for a family history of sudden death or ventricular arrhythmia) and physical exam should be obtained to assess for the presence of cardiac disease. In patients with relevant risk factors and based on the clinician’s judgment, further cardiovascular evaluation may be considered (e.g., electrocardiogram and echocardiogram). Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during ADHD treatment should undergo a prompt cardiac evaluation.
Vascular
Peripheral Vasculopathy, Including Raynaud’s Phenomenon
Stimulants used to treat ADHD, such as methylphenidate hydrochloride extended release tablets, are associated with peripheral vasculopathy, including Raynaud’s phenomenon. Signs and symptoms are usually intermittent and mild; however, very rare sequelae include digital ulceration and/or soft tissue breakdown. Effects of peripheral vasculopathy, including Raynaud’s phenomenon, were observed in post-marketing reports at different times and at therapeutic doses in all age groups throughout the course of treatment. Signs and symptoms generally improve after reduction in dose or discontinuation of drug. Careful observation for digital changes is necessary during treatment with ADHD stimulants. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients.
Dependence/Tolerance
Drug Dependence
APO-METHYLPHENIDATE ER contains methylphenidate, a Schedule III Controlled Substance. APO-METHYLPHENIDATE ER should be given cautiously to patients with a history of drug dependence or alcoholism. Chronic abusive use can lead to marked tolerance and psychological dependence with varying degrees of abnormal behaviour. Frank psychotic episodes can occur, especially with parenteral abuse (see 4.4 Administration). Careful supervision is required during withdrawal from abuse since severe depression may occur. Withdrawal following chronic therapeutic use may unmask symptoms of an underlying disorder that may require follow-up (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Driving and Operating Machinery
Because methylphenidate may affect performance, due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery. Patients should be cautioned accordingly until they are reasonably certain that APO-METHYLPHENIDATE ER does not adversely affect their ability to engage in such activities.
Endocrine and Metabolism
Thyrotoxicosis
APO-METHYLPHENIDATE ER is contraindicated in patients with thyrotoxicosis (see 2 CONTRAINDICATIONS)
Long-Term Suppression of Growth
Sufficient data on the safety of long-term use of methylphenidate in children are not yet available. Although a causal relationship has not been established, suppression of growth (i.e., weight gain and/or height) has been reported with the long-term use of stimulants in children. Therefore, patients requiring long-term therapy should be carefully monitored. Patients who are not growing or gaining weight as expected should have their treatment interrupted.
Gastrointestinal
Potential for Gastrointestinal Obstruction
Because the APO-METHYLPHENIDATE ER tablet does not appreciably change in shape in the gastrointestinal tract, APO-METHYLPHENIDATE ER should not be administered to patients with pre-existing gastrointestinal narrowing (pathologic or iatrogenic, such as small bowel inflammatory disease, “short gut” syndrome due to adhesions or decreased transit time, past history of peritonitis, cystic fibrosis, chronic intestinal pseudo-obstruction, or Meckel’s diverticulum). There have been rare reports of obstructive symptoms in patients with known strictures in association with the ingestion of other drugs in non-deformable controlled-release formulations. There have been very rare reports of obstructive symptoms associated with the use of methylphenidate hydrochloride extended-release tablets in patients without known gastrointestinal stricture. Due to the controlled-release design, APO-METHYLPHENIDATE ER tablets should only be used in patients who are able to swallow the tablets whole (see 4.4 Administration).
Monitoring and Laboratory Tests
Periodic laboratory tests are advised during prolonged therapy. The tests should include, but not be limited to, haematological parameters, including complete blood count, differential and platelet counts, and liver enzymes.
Neurologic
Cerebrovascular disorders
Cerebrovascular disorders (including cerebral vasculitis and cerebral hemorrhage) have been reported with the use of methylphenidate hydrochloride extended-release tablets. Consider cerebrovascular disorders as a possible diagnosis in any patient who develops new neurological symptoms that are consistent with cerebral ischemia during APO-METHYLPHENIDATE ER therapy. These symptoms could include severe headache, unilateral weakness or paralysis, and impairment of coordination, vision, speech, language, or memory. If a cerebrovascular disorder is suspected during treatment, discontinue APO-METHYLPHENIDATE ER immediately. Early diagnosis may guide subsequent treatment (see 8.5 Post-Market Adverse Reactions).
In patients with pre-existing cerebrovascular disorders (e.g., aneurysm, vascular malformations/anomalies), treatment with APO-METHYLPHENIDATE ER is not recommended.
Motor and Verbal Tics, and Worsening of Tourette’s Syndrome
Central nervous system (CNS) stimulants, including methylphenidate, have been associated with the onset or exacerbation of motor and verbal tics. Worsening of Tourette’s syndrome has also been reported. It is recommended that the family history be assessed, and that the patient is clinically evaluated for tics or Tourette’s syndrome before initiating methylphenidate. Regular monitoring for the emergence or worsening of tics or Tourette’s syndrome during treatment with methylphenidate is recommended at every dose adjustment and every visit, and treatment discontinued if clinically appropriate (see 8.2 Clinical Trial Adverse Reactions, Tics).
Serotonin toxicity / Serotonin syndrome
Serotonin toxicity also known as serotonin syndrome is a potentially life-threatening condition and has been reported with methylphenidate, including methylphenidate hydrochloride extended-release tablets, with concomitant use of serotonergic or dopaminergic drugs (see 9 DRUG INTERACTIONS).
Serotonin toxicity is characterised by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with APO-METHYLPHENIDATE ER and other serotonergic agents is clinically warranted, careful observation of the patient is advised (see 9 DRUG INTERACTIONS). If serotonin toxicity is suspected, treatment with APO-METHYLPHENIDATE ER (and serotonergic drugs) must be immediately discontinued and appropriate treatment instituted.
Ophthalmologic
Increased intraocular pressure and glaucoma
There have been reports of elevation of intraocular pressure (IOP) and glaucoma associated with methylphenidate treatment. APO-METHYLPHENIDATE ER is contraindicated in patients with glaucoma (see 2 CONTRAINDICATIONS).
Psychiatric
Aggression, Anxiety and Agitation
Aggressive behaviour, marked anxiety or agitation are often observed in patients with ADHD, and have been reported in patients treated with methylphenidate hydrochloride extended-release tablets (see 8.2 Clinical Trial Adverse Reactions). Anxiety led to discontinuation of methylphenidate hydrochloride extended-release tablets in some patients. It is recommended to monitor patients beginning treatment with APO-METHYLPHENIDATE ER for the appearance of, or worsening of, aggressive behaviour, marked anxiety or agitation, in which case consider discontinuing methylphenidate.
Emergence of New Psychotic or Manic Symptoms
Treatment emergent psychotic or manic symptoms, e.g., hallucinations, delusional thinking, or mania in children and adolescents without a prior history of psychotic illness or mania, can be caused by stimulants at usual doses. If such symptoms occur, consideration should be given to a possible causal role of the stimulant, and discontinuation of treatment may be appropriate. In a pooled analysis of multiple short-term, placebo-controlled studies, such symptoms occurred in about 0.1% (4 patients with events out of 3482 exposed to methylphenidate or amphetamine for several weeks at usual doses) of stimulant-treated patients compared to 0 in placebo-treated patients.
Pre-Existing Psychosis
Administration of stimulants may exacerbate symptoms of behaviour disturbance and thought disorder in patients with a pre-existing psychotic disorder.
Screening Patients for Bipolar Disorder
Particular care should be taken in using stimulants to treat ADHD in patients with comorbid bipolar disorder because of concern for possible induction of a mixed/manic episode in such patients. Prior to initiating treatment with a stimulant, patients with comorbid depressive symptoms should be adequately screened to determine if they are at risk for bipolar disorder; such screening should include a detailed psychiatric history, including a family history of suicide, bipolar disorder, and depression.
Suicidal Behaviour and Ideation
There have been post-marketing reports of suicide-related events in patients treated with ADHD drugs, including cases of ideation, attempts, and very rarely, completed suicide. The mechanism of this risk is not known. ADHD and its related co-morbidities may be associated with increased risk of suicidal ideation and/or behaviour.
Therefore, it is recommended for patients treated with ADHD drugs that caregivers and physicians monitor for signs of suicide-related behaviour, including at dose initiation/optimization and drug discontinuation. Patients should be encouraged to report any distressing thoughts or feelings at any time to their healthcare professional. Patients with emergent suicidal ideation and behaviour should be evaluated immediately. The physician should initiate appropriate treatment of the underlying psychiatric condition and consider a possible change in the ADHD treatment regimen (see 8.5 Post-Market Adverse Reactions).
Reproductive Health: Female and Male Potential
- Function
Priapism
Prolonged and painful erections requiring immediate medical attention (sometimes including surgical intervention), have been reported with methylphenidate products, including methylphenidate hydrochloride extended-release tablets in both pediatric and adult patients (see 8.5 Post-Market Adverse Reactions). Priapism can develop after some time on methylphenidate, often subsequent to an increase in dose. Priapism has also appeared during a period of methylphenidate withdrawal (drug holidays or during discontinuation). Patients who develop abnormally sustained erections or frequent and painful erections should seek immediate medical attention.
- Teratogenic Risk
Methylphenidate hydrochloride has been shown to have teratogenic effects in rabbits when given in doses of 200 mg/kg/day, which is approximately 100 times and 40 times the maximum recommended human dose on a mg/kg and mg/m2 basis, respectively.
Teratogenic effects were not seen in rats at methylphenidate hydrochloride doses up to 30 mg/kg/day, resulting in a systemic exposure to methylphenidate of approximately seven times that seen in trials in adult and adolescent volunteers and patients receiving daily dose of 72 mg of methylphenidate hydrochloride, based on pharmacokinetic data.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Methylphenidate hydrochloride extended-release tablets should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
7.1.2 Breast-feeding
Methylphenidate has been detected in human milk. Based on breast milk sampling from five mothers, methylphenidate concentrations in human milk resulted in infant doses of 0.16% to 0.7% of the maternal weight adjusted dosage, and a milk to maternal plasma ratio ranging between 1.1 and 2.7 (see 10 CLINICAL PHARMACOLOGY). Caution should be exercised if APO-METHYLPHENIDATE ER is administered to a breast-feeding woman.
There is one case report of an infant who experienced an unspecified decrease in weight during the period of exposure but recovered and gained weight after the mother discontinued treatment with methylphenidate. A risk to the suckling child cannot be excluded. A decision should be made whether to abstain from breast-feeding or to abstain from APO-METHYLPHENIDATE ER therapy, taking into account the benefit of breast-feeding to the child and the benefit of therapy to the mother.
7.1.3 Pediatrics
Pediatrics (6 to 18 years of age): Long-term effects of methylphenidate in children have not been well established (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Pediatrics (< 6 years of age): APO-METHYLPHENIDATE ER should not be used in children under six years of age. No data are available to Health Canada; therefore, Health Canada has not authorized an indication for children under six years of age.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for geriatric use.
8 ADVERSE REACTIONS
8.1 Adverse Reactions Overview
The development program for methylphenidate hydrochloride extended-release tablets included exposures of 321 pediatric patients, and 305 adult patients to the drug in placebo-controlled, double-blind trials, and 3590 pediatric and adult patients in open-label clinical trials. The patients in these studies received methylphenidate hydrochloride extended-release tablets 18, 36, 54 or 72 mg/day. Children, adolescents, and adults with ADHD were evaluated in five placebo-controlled clinical studies (Studies 1, 2, and 3 in children; Study 4 in adolescents; Study 5 in adults), three open-label clinical trials and two open-label extensions. A limited number of adolescents and adults received methylphenidate hydrochloride extended-release tablets 72 mg/day (n=85) and 90 mg/day (n=41), respectively. Safety was assessed by collecting adverse events, results of physical examinations, vital signs, weights, laboratory analyses, and ECGs.
Adverse events during exposure were obtained primarily by general inquiry and recorded by clinical investigators using terminology of their own choosing. Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse events without first grouping similar types of events into a smaller number of standardized event categories. In the tables and listings that follow, COSTART terminology has been used to classify reported adverse events, except for Study 5 in adults, where MedDRA terminology was used.
The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed. An event was considered treatment emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
The most common adverse events reported in clinical trials in greater than 10% of patients were headache, dry mouth, nausea, weight decreased, decreased appetite, insomnia and upper respiratory tract infection.
Adverse Events Leading to Discontinuation of Treatment
Placebo-controlled Trials
In a 4-week, placebo-controlled, parallel-group trial (Study 3), one patient treated with methylphenidate hydrochloride extended-release tablets (0.9%; 1/106), one methylphenidate t.i.d.-treated patient (0.9%; 1/107), and one placebo-treated patient (1.0%; 1/99) discontinued due to an adverse event (sadness, emotional lability, and increase in tics, respectively).
In the 2-week placebo-controlled phase of a trial in adolescents (Study 4), no patients treated with methylphenidate hydrochloride extended-release tablets (0%; 0/87) and 1 placebo-treated patient (1.1%; 1/90) discontinued due to an adverse event (increased mood irritability).
In the 5-week placebo-controlled phase of a trial in adults (Study 5), 0% (0/96) of the patients in the placebo group, 1.0% (1/101) of the patients in the methylphenidate hydrochloride extended-release tablets 18 mg dose group, 2.9% (3/102) of the patients in the methylphenidate hydrochloride extended-release tablets 36 mg dose group and 7.8% (8/102) of the patients in the methylphenidate hydrochloride extended-release tablets 72 mg dose group discontinued due to an adverse event.
Open-Label Trials
In two open-label, long-term safety trials (Studies 6 and 7), one study up to 27 months in children aged 6 to 13 and one study up to 9 months in child, adolescent and adult patients treated with methylphenidate hydrochloride extended-release tablets, 6.7% (101/1514) of patients discontinued due to adverse events. Those events leading to discontinuation of methylphenidate hydrochloride extended-release tablets, with an incidence of >0.5%, included: insomnia (1.5%), twitching (tics, 1.0%), nervousness (0.7%), emotional lability (0.7%), abdominal pain (0.7%), and anorexia (0.7%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse Events Occurring in Placebo-Controlled Trials in Adults
Table 4 lists the incidence of treatment-emergent adverse events for a 5-week placebo-controlled trial (Study 5) in adults with ADHD at methylphenidate hydrochloride extended-release tablets doses of 18, 36, or 72 mg/day.
Table 4: Incidence (%) of Treatment-Emergent Events1 in a 5-Week Placebo-Controlled Clinical Trial of Methylphenidate Hydrochloride Extended-Release Tablets in Adults
| Body System | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets | Placebo | ||
18 mg q.d. (n=101) | 36 mg q.d. (n=102) | 72 mg q.d. (n=102) | q.d. (n=96) | ||
| Cardiac Disorders | Palpitations | 2 | 5 | 5 | 0 |
| Tachycardia | 4 | 5 | 8 | 0 | |
| Ear and Labyrinth Disorders | Vertigo | 2 | 3 | 2 | 0 |
| Body System | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets | Placebo | ||
18 mg q.d. (n=101) | 36 mg q.d. (n=102) | 72 mg q.d. (n=102) | q.d. (n=96) | ||
| Gastrointestinal Disorders | Abdominal pain upper | 4 | 2 | 2 | 5 |
| Diarrhea | 3 | 1 | 4 | 5 | |
| Dry mouth | 8 | 7 | 21 | 2 | |
| Hemorrhoids | 0 | 0 | 4 | 0 | |
| Nausea | 8 | 16 | 15 | 4 | |
General Disorders and Administration Site Conditions | Fatigue | 4 | 4 | 6 | 6 |
| Infectious and Infestations | Influenza | 4 | 2 | 2 | 3 |
| Nasopharyngitis | 7 | 8 | 4 | 9 | |
| Investigations | Weight decreased | 3 | 8 | 11 | 5 |
| Metabolism and Nutrition Disorders | Decreased appetite | 20 | 22 | 34 | 7 |
| Nervous System Disorders | Confusional state | 0 | 3 | 1 | 0 |
| Dizziness | 6 | 10 | 9 | 7 | |
| Headache | 26 | 21 | 17 | 18 | |
| Initial insomnia | 3 | 2 | 5 | 2 | |
| Insomnia | 12 | 12 | 17 | 7 | |
| Migraine | 0 | 1 | 3 | 3 | |
| Paresthesia | 3 | 1 | 1 | 0 | |
| Tremor | 1 | 1 | 7 | 1 | |
| Psychiatric Disorders | Aggression | 2 | 3 | 2 | 1 |
| Agitation | 0 | 1 | 3 | 1 | |
| Anxiety | 3 | 5 | 8 | 1 | |
Attention deficit/ Hyperactivity disorder | 0 | 0 | 4 | 0 | |
| Depressed mood | 6 | 3 | 5 | 1 | |
| Depression | 0 | 3 | 4 | 1 | |
| Irritability | 4 | 4 | 9 | 1 | |
| Nervousness | 0 | 3 | 8 | 1 | |
| Restlessness | 0 | 2 | 6 | 0 | |
| Tension | 0 | 3 | 0 | 0 | |
| Respiratory, Thoracic and Mediastinal Disorders | Pharyngolaryngeal pain | 2 | 0 | 4 | 1 |
| Skin and Subcutaneous Tissue Disorders | Hyperhidrosis | 5 | 3 | 8 | 1 |
| Body System | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets | Placebo | ||
18 mg q.d. (n=101) | 36 mg q.d. (n=102) | 72 mg q.d. (n=102) | q.d. (n=96) | ||
| Vascular Disorders | Hypertension | 0 | 1 | 4 | 4 |
1 Events, regardless of causality, for which the incidence in any methylphenidate hydrochloride extended-release tablets dosage group was at least 2%. Incidence has been rounded to the nearest whole number. 2 MedDRA Terms | |||||
Adverse Events Occurring in Long-Term Safety Trials
Methylphenidate hydrochloride extended-release tablets was evaluated in two long-term open-label studies (n=1514), one study up to 27 months in children aged 6 to 13 and one study up to 9 months in child, adolescent and adult patients. The adverse event profile seen is similar to that observed in shorter term trials. COSTART terminology is used to classify reported adverse experiences. The experiences are classified within body system categories and grouped by frequency.
Table 5: Adverse Events Occurring in Long-Term Safety Trials
| Frequency | Very Frequent | Frequent | Less Frequent | |
| Body System | >10% - <50% | 5-10% | <5% and ≥1% | <1% |
| Body as a Whole | headache | accidental injury, abdominal pain, fever | flu syndrome, allergic reaction, infection, aggravation reaction, pain, extremity pain, back pain | surgery procedure, accidental overdose, chest pain, cyst, infection fungal, photosensitivity reaction, malaise, asthenia, neck pain |
| Cardiovascular System | hypertension | cardiovascular disorder, tachycardia, migraine | ||
| Digestive System | anorexia, vomiting | gastroenteritis, diarrhea, nausea, dyspepsia | rectal disorder, gastritis, increased appetite, nausea and vomiting, periodontal abscess, tongue disorder, tooth disorder, constipation | |
| Endocrine System | diabetes mellitus | |||
| Hemic and | ecchymosis, petechia, |
| Frequency | Very Frequent | Frequent | Less Frequent | |||||
| Body System | >10% - <50% | 5-10% | <5% and ≥1% | <1% | ||||
| Lymphatic System | lymphadenopathy | |||||||
Metabolic and Nutritional System | weight loss | Dehydration | ||||||
Musculoskeletal System | myalgia | arthralgia, leg cramps | ||||||
| Nervous System | insomnia | twitching, nervousness, emotional lability, anxiety, depression, somnolence, hostility, dizziness | apathy, neurosis, hallucinations, speech disorder, sleep disorder, tremor, thinking abnormal, abnormal dreams | |||||
| Respiratory System | upper respiratory tract infection | pharyngitis, cough increased, rhinitis | sinusitis, respiratory disorder, asthma bronchitis, epistaxis | dyspnea, pneumonia, voice alterations, laryngitis | ||||
| Skin System | rash, contact dermatitis | pustular rash, urticaria, eczema, pruritus, skin benign neoplasm, acne, alopecia, nail disorder, psoriasis, herpes simplex | ||||||
| Special Senses | otitis media | conjunctivitis | ear disorder, diplopia, ear pain | |||||
| Urogenital System | albuminuria, urinary frequency, urinary tract infection, urinary urgency | |||||||
Adverse Events Occurring in Open-Label Adult Trials
In addition to the adverse events listed above, the following ADRs were reported in adult patients treated with methylphenidate hydrochloride extended-release tablets in open-label clinical trials of up to one year.
Table 6: Adverse Drug Reactions reported by Methylphenidate Hydrochloride Extended-Release Tablets -Treated Subjects in 5 Open-Label Clinical Trials of Adult Subjects
| Frequency | Very Frequent | Frequent | Less Frequent | |
| Body System | >10% - <50% | 5-10% | <5% and ≥1% | <1% |
| Blood and Lymphatic System Disorders | leukopenia | |||
| Cardiac Disorders | palpitations | |||
| Eye Disorders | vision blurred | accommodation disorder, dry eye | ||
| Gastrointestinal Disorders | dry mouth | abdominal pain upper, abdominal discomfort | ||
| General Disorders and Administration Site Conditions | irritability, fatigue | feeling jittery, pyrexia | thirst | |
| Infections and Infestations | nasopharyngitis | |||
| Investigations | blood pressure increased, heart rate increased | alanine aminotransferase increased | ||
| Metabolism and Nutrition disorders | decreased appetite | |||
| Musculoskeleta l and Connective Tissue Disorders | muscle spasms, muscle tightness | |||
| Nervous System Disorder | psychomotor hyperactivity, paraesthesia | tension headache, sedation, lethargy, | ||
| Psychiatric Disorders | restlessness | Agitation, depressed mood, initial insomnia, libido decreased | affect lability, aggression, anger, bruxism, hypervigilance, mood altered, mood swings, panic attack, tearfulness, tension, confusional state | |
| Reproductive system and Breast | erectile dysfunction |
| Frequency | Very Frequent | Frequent | Less Frequent | |||||
| Body System | >10% - <50% | 5-10% | <5% and ≥1% | <1% | ||||
| Disorders | ||||||||
| Respiratory, Thoracic and Mediastinal Disorders | oropharyngeal pain | |||||||
Skin and Subcutaneous Tissue Disorder | hyperhidrosis | |||||||
| Vascular Disorders | hot flush | |||||||
Tics
During two long-term, open-label studies, the overall incidence of tics (twitching) in children was 4.3% (48/1109 subjects). In one study, the incidence of tics rose from 3% at baseline to 5% after one month. The incidence remained the same during the rest of the study. The treatment period was up to 27 months with a mean treatment duration of 10.3 months.
In a long-term study of up to 9 months of treatment, the incidence of tics was 0.4% (1/269) in adolescents and 0.7% (1/136) in adults.
Logorrhea
Logorrhea was observed as an uncommon adverse reaction in all clinical trials (including open-label trials, adult and pediatric)
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Adverse Events Occurring in Placebo-Controlled Trials in Children
Table 7 enumerates, for the 4-week placebo-controlled, parallel-group trial in children with ADHD at methylphenidate hydrochloride extended-release tablets doses of 18, 36, or 54 mg q.d., the incidence of treatment-emergent adverse events. The table includes only those events that occurred in 1% or more of patients treated with methylphenidate Hydrochloride extended release tablets, methylphenidate hydrochloride and placebo-treated patients.
Table 7: Incidence (%) of Treatment-Emergent Events1 in a 4-Week Placebo-Controlled Clinical Trial of Methylphenidate Hydrochloride Extended-Release Tablets in Children
| Body Systems | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets q.d. (n=106) | Methylphenidate hydrochloride t.i.d. (n=107) | Placebo (n=99) |
| General | Headache | 14 | 6 | 10 |
| Abdominal pain | 7 | 6 | 1 | |
| Aggravation reaction | 2 | 2 | 2 | |
| Digestive | Vomiting | 4 | 2 | 3 |
| Anorexia | 4 | 0 | 0 | |
| Nervous | Insomnia | 4 | 1 | 1 |
| Dizziness | 2 | 0 | 0 | |
| Respiratory | Upper respiratory tract infection | 8 | 7 | 5 |
| Cough increased | 4 | 8 | 2 | |
| Pharyngitis | 4 | 4 | 3 | |
| Sinusitis | 3 | 1 | 0 |
1Events, regardless of causality, for which the incidence for patients treated with methylphenidate hydrochloride extended-release tablets was at least 1%. Incidence greater than 1% has been rounded to the nearest whole number.
2COSTART terms
Adverse Events Occurring in Placebo-Controlled Trials in Adolescents
Table 8 lists the incidence of treatment-emergent adverse events for a 2-week placebo- controlled trial (Study 4) in adolescents with ADHD at methylphenidate hydrochloride extended-release tablets doses of 18, 36, 54 or 72 mg/day.
Table 8: Incidence (%) of Treatment-Emergent Events1 in a 2-Week Placebo-Controlled Clinical Trial of Methylphenidate Hydrochloride Extended-Release Tablets in Adolescents
| Body Systems | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets, q.d. (n=87) | Placebo (n=90) |
| General | Abdominal pain | 2 | 2 |
| Accidental injury | 6 | 3 | |
| Allergic reaction | 1 | 0 | |
| Asthenia | 2 | 2 | |
| Chest pain | 1 | 0 | |
| Fever | 3 | 0 | |
| Flu syndrome | 1 | 0 |
| Body Systems | Preferred Term2 | Methylphenidate Hydrochloride Extended-Release Tablets, q.d. (n=87) | Placebo (n=90) |
| Headache | 9 | 8 | |
| Infection | 1 | 6 | |
| Pain | 1 | 1 | |
| Digestive | Anorexia | 2 | 0 |
| Diarrhea | 2 | 0 | |
| Dyspepsia | 1 | 0 | |
| Gastrointestinal Disorder | 1 | 0 | |
| Increased appetite | 1 | 0 | |
| Nausea | 1 | 2 | |
| Tooth caries | 1 | 0 | |
| Vomiting | 3 | 0 | |
| Musculoskeletal | Myalgia | 1 | 0 |
| Nervous | Agitation | 1 | 0 |
| Anxiety | 1 | 0 | |
| Dizziness | 1 | 0 | |
| Insomnia | 4 | 0 | |
| Neurosis | 1 | 1 | |
| Tremor | 1 | 0 | |
| Respiratory | Pharyngitis | 2 | 1 |
| Rhinitis | 3 | 2 | |
| Urogenital | Dysmenorrhea | 2 | 0 |
1 Events, regardless of causality, for which the incidence for patients treated with methylphenidate hydrochloride extended-release tablets was at least 1%. Incidence has been rounded to the nearest whole number.
2 COSTART terms
8.3 Less Common Clinical Trial Adverse Reactions
Treatment emergent adverse events occurring in <1% of patients treated with methylphenidate hydrochloride extended-release tablets in open-label trials are listed in Table 5 and Table 6.
8.5 Post-Market Adverse Reactions
Adverse events identified during post-marketing experience with methylphenidate hydrochloride extended-release tablets are included in Table 9.
In each table, the frequencies are provided according to the following convention:
Very common ≥1/10
Common ≥1/100 to <1/10
Uncommon ≥1/1,000 to <1/100
Rare ≥1/10,000 to <1/1,000
Very rare <1/10,000, including isolated reports
Table 9: Adverse Events Identified During Post-marketing Experience with Methylphenidate Hydrochloride Extended-Release Tablets
Blood and Lymphatic System Disorders Very rare Pancytopenia, Thrombocytopenia, Thrombocytopenic purpura, Aplastic anemia Cardiac Disorders Very rare Arrhythmia Immune System Disorders Rare Hypersensitivity reactions such as Angioedema, Anaphylactic reactions, Auricular swelling, Bullous conditions, Exfoliative conditions, Urticarias, Pruritus NEC, Rashes, Eruptions and Exanthemas NEC, Serum sickness Psychiatric Disorders Very rare Disorientation, Hallucination, Hallucination auditory, Hallucination visual, Mania, Complete Suicide, Suicide ideation, Suicide attempt, Psychotic disorder, Logorrhea, Libido disorder, New-onset or worsening obsessive-compulsive disorders and symptoms (including trichotillomania, obsessive thoughts, compulsions) Nervous System Disorders Very rare Convulsion, Grand mal convulsion, Dyskinesia Very rare Cerebrovascular disorder (including Cerebral vasculitis, Cerebral hemorrhage, Cerebral arteritis, Cerebral vascular occlusion) Eye Disorders Very rare Diplopia, Mydriasis, Visual impairment Cardiac Disorders Very rare Angina pectoris, Bradycardia, Extrasystoles, Supraventricular tachycardia, Ventricular extrasystoles Vascular Disorders Very rare Raynaud’s phenomenon Respiratory, thoracic and mediastinal disorders Unknown Epistaxis Hepatobiliary Disorders Very rare Blood alkaline phosphatase increased, Blood bilirubin increased, Hepatic enzyme increased, Hepatocellular injury, Acute hepatic failure Skin and Subcutaneous Tissue Disorders Very rare Alopecia, Erythema, Dermatitis exfoliative, Stevens-Johnson Syndrome |
|---|
Musculoskeletal and Connective Tissue Disorders Very rare Arthralgia, Myalgia, Muscle twitching, Rhabdomyolysis Unknown Trismus Renal and Urinary Disorders Unknown Incontinence Reproductive System and Breast Disorders Very Rare Priapism Rare Gynecomastia General Disorders and Administration Site Conditions Rare Therapeutic response decreased Very rare Chest pain, Chest discomfort, Drug effect decreased, Hyperpyrexia, Sudden cardiac death Investigations Very rare Platelet count decreased, White blood cell count abnormal Gastrointestinal Disorders Very rare Pancreatitis Endocrine Disorders Very rare Hypoglycemia |
|---|
Adverse Events with Other Methylphenidate Hydrochloride Products
Nervousness and insomnia are the most common adverse reactions reported with other methylphenidate products. Other reactions include hypersensitivity (including skin rash, urticaria, fever, arthralgia, exfoliative dermatitis, erythema multiforme with histopathological findings of necrotizing vasculitis, and thrombocytopenic purpura); anorexia; nausea; dizziness; headache; dyskinesia; drowsiness; blood pressure and pulse changes, both up and down; tachycardia; angina; abdominal pain; and weight loss during prolonged therapy. There have been rare reports of Tourette’s syndrome. Toxic psychosis has been reported. Although a definite causal relationship has not been established, the following have been reported in patients taking this drug: instances of abnormal liver function, e.g., hepatic coma; isolated cases of cerebral arteritis and/or occlusion; leukopenia and/or anemia; transient depressed mood; and a few instances of scalp hair loss. There have been reports of serotonin syndrome following coadministration of methylphenidate with serotonergic drugs. Very rare reports of neuroleptic malignant syndrome (NMS) have been received, and in most of these, patients were concurrently receiving therapies associated with NMS. In a single report, a ten-year-old boy who had been taking methylphenidate for approximately 18 months experienced an NMS-like event within 45 minutes of ingesting his first dose of venlafaxine. It is uncertain whether this case represented a drug- drug interaction, a response to either drug alone, or some other cause.
Suicidal Behaviour and Ideation
There have been post-marketing reports of suicide-related events, including completed suicide, suicide attempt, and suicidal ideation in patients treated with ADHD drugs. In some of these reports, comorbid conditions may have contributed to the event. (see 7 WARNINGS AND
PRECAUTIONS, Suicidal Behaviour and Ideation)
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
|
|---|
9.2 Drug Interactions Overview
Because of possible increases in blood pressure and heart rate, APO-METHYLPHENIDATE ER should be used cautiously with drugs with similar pharmacological actions.
9.3 Drug-Behavioural Interactions
Alcohol may exacerbate the CNS adverse effect of psychoactive drugs. Therefore, patients undergoing APO-METHYLPHENIDATE ER therapy should be advised to avoid alcohol during treatment.
9.4 Drug-Drug Interactions
Vasopressor Agents
Because of possible increases in blood pressure, APO-METHYLPHENIDATE ER should be used cautiously with vasopressor agents (see 7 WARNINGS AND PRECAUTIONS, Hypertension and Other Cardiovascular Conditions).
Inhibition of Drug Metabolism by Methylphenidate
Human pharmacologic studies have shown that methylphenidate may inhibit the metabolism of coumarin anticoagulants (e.g., warfarin), anticonvulsants (e.g., phenobarbital, phenytoin, primidone) and some antidepressants (tricyclics and selective serotonin reuptake inhibitors). Downward dose adjustment of these drugs may be required when given concomitantly with methylphenidate. It may be necessary to adjust the dosage and monitor plasma drug concentrations (or, in the case of coumarin, coagulation times) when initiating or discontinuing concomitant methylphenidate.
Antihypertensives
APO-METHYLPHENIDATE ER may decrease the effectiveness of drugs used to treat hypertension. It is recommended to monitor blood pressure and adjust the dosage of the antihypertensive drug as needed (see 7 WARNINGS AND PRECAUTIONS, Hypertension and Other Cardiovascular Conditions).
Halogenated Anesthetics
Concomitant use of halogenated anesthetics and APO-METHYLPHENIDATE ER may increase the risk of sudden blood pressure and heart rate increase during surgery. It is recommended to avoid use of APO-METHYLPHENIDATE ER in patients being treated with anesthetics on the day of surgery.
Antipsychotics
Because a predominant action of methylphenidate is to increase extracellular dopamine levels, APO-METHYLPHENIDATE ER may be associated with pharmacodynamic interactions when co-administered with some antipsychotics. Caution is warranted in patients receiving both APO-METHYLPHENIDATE ER and an antipsychotic, as extrapyramidal symptoms could emerge when these drugs are administered concomitantly or when adjusting the dosage of one or both drugs.
Serotonergic Drugs
There have been reports of serotonin syndrome with methylphenidate, including methylphenidate hydrochloride extended-release tablets, with concomitant use of serotonergic drugs. If concomitant treatment with APO-METHYLPHENIDATE ER and other serotonergic agents is clinically warranted, careful observation of the patient is advised (see 7 WARNINGS AND PRECAUTIONS, Serotonin toxicity / Serotonin syndrome). If serotonin toxicity is suspected, APO-METHYLPHENIDATE ER (and serotonergic drugs) must be immediately discontinued and appropriate treatment instituted.
Monoamine Oxidase Inhibitors
Methylphenidate is contraindicated during treatment with monoamine oxidase inhibitors, and also within a minimum of 14 days following discontinuation of a monoamine oxidase inhibitor (hypertensive crises may result). The same precautions apply to APO-METHYLPHENIDATE ER (see 2 CONTRAINDICATIONS).
Clonidine
Serious adverse events, including sudden death, have been reported in concomitant use with clonidine. In these cases, no causality for the combination could be established because of insufficient data.
9.5 Drug-Food Interactions
There are no known food interactions with methylphenidate hydrochloride extended-release tablets. (see 10.3 Pharmacokinetics, Food Effect).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Methylphenidate hydrochloride is a central nervous system (CNS) stimulant. The mechanism of action on the CNS is not completely understood, but methylphenidate is thought to block the reuptake of dopamine and norepinephrine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
10.2 Pharmacodynamics
Methylphenidate is a racemic mixture comprised of the d- and l-isomers. The d-isomer is pharmacologically active; the l-isomer has little pharmacologic activity. Following administration of methylphenidate hydrochloride extended-release tablets, plasma concentrations of the l-isomer were approximately 1/40th the plasma concentrations of the d-isomer.
Non-Clinical Pharmacodynamics
Methylphenidate hydrochloride is a sympathomimetic agent classified as a central nervous system (CNS) stimulant. Its mechanism of action is not entirely understood; however, it blocks the reuptake and enhances the release of dopamine and norepinephrine in the mammalian brain, an effect that increases dopamine and norepinephrine levels in the synaptic cleft. In vitro radioligand binding studies demonstrate that binding of methylphenidate in the brain is localized to dopamine-rich areas. Methylphenidate releases dopamine from a reserpine-sensitive storage pool and inhibits the catecholamine metabolic enzyme, monoamine oxidase (MAO), in the brain of rats.
In a number of animal models, methylphenidate enhances locomotor activity and induces stereotypic behaviours. Recent clinical findings in ADHD children suggest an abnormality in the dopamine transporter gene (DAT1), the D4 receptor gene (DRD-4) and/or the D2 receptor gene that may be at least partly overcome by the dopaminergic effects of methylphenidate, suggesting a possible mode of action.
Safety Pharmacology
Methylphenidate hydrochloride had no effect in hERG-transfected cells or on the action potential of guinea pig papillary muscles. The no observed adverse effect level (NOAEL) for stimulatory effects on the cardiovascular system in conscious dogs (increased blood pressure and heart rate) was 10 mg/kg. The NOAEL for stimulatory effects on the respiratory system in free-moving rats was 3 mg/kg. The NOAEL for methylphenidate hydrochloride’s convulsion evoking action in mice was 10 mg/kg.
10.3 Pharmacokinetics
Absorption:
Methylphenidate is readily absorbed. Following oral administration of methylphenidate hydrochloride extended-release tablets, plasma methylphenidate concentrations reach an initial maximum at about 1 hour followed by gradual ascending concentrations over the next 5 to 9 hours. Mean times to reach peak plasma concentrations across all doses of methylphenidate hydrochloride extended-release tablets occurred between 6 to 10 hours. Methylphenidate hydrochloride extended-release tablets once daily (q.d.) minimizes the fluctuations between peak and trough concentrations associated with multiple doses of immediate-release methylphenidate treatments (see Figure 1). The relative bioavailability of methylphenidate hydrochloride extended-release tablets q.d. and methylphenidate three times a day (t.i.d.) in adults is comparable.
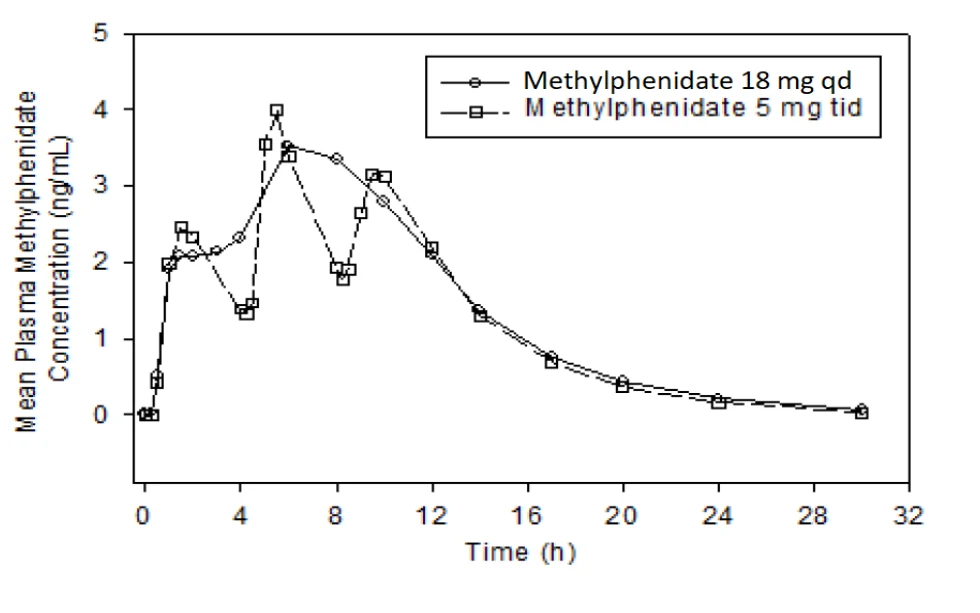
Figure 1: Mean methylphenidate plasma concentrations in 36 fasted adults, following a single dose of methylphenidate hydrochloride extended-release tablets 18 mg q.d. and immediate-release methylphenidate hydrochloride 5 mg t.i.d. administered every 4 hours.
Children (Single Dose)
The mean pharmacokinetic parameters in 13 children 7 to 12 years of age following administration of methylphenidate hydrochloride extended-release tablets 18, 36 or 54 mg are summarized in Table 10.
Table 10: Summary of Methylphenidate Hydrochloride Extended-Release Tablets Pharmacokinetic Parameters in Children after Single Dosing (Mean ± SD)
| n | Cmax (ng/mL) | Tmax (h) | AUC0-11.5 (ng·h/mL)1 | |
|---|---|---|---|---|
| Methylphenidate hydrochloride extended- | 3 | 6.0 ± 1.3 | 9.4 ± 0.02 | 50.4 ± 7.8 |
| n | Cmax (ng/mL) | Tmax (h) | AUC0-11.5 (ng·h/mL)1 | ||
|---|---|---|---|---|---|
| release tablets 18 mg | |||||
| Methylphenidate hydrochloride extended-release tablets 36 mg | 7 | 11.3 ± 2.6 | 8.1 ± 1.1 | 87.7 ± 18.2 | |
| Methylphenidate hydrochloride extended-release tablets 54 mg | 3 | 15.0 ± 3.8 | 9.1 ± 2.5 | 121.5 ± 37.3 | |
- 1. limited blood sampling
Adolescents (Steady-State)
The pharmacokinetics of methylphenidate were evaluated in adolescents 13 to 16 years of age with ADHD following steady-state dosing with methylphenidate hydrochloride extended-release tablets 36 mg, 54 mg, or 72 mg. The mean pharmacokinetic parameters are summarized in Table 11.
Table 11: Summary of Methylphenidate Hydrochloride Extended-Release Tablets Pharmacokinetic Parameters in Adolescents at Steady-State (Mean ± SD)
| n | Cmax (ng/mL) | Tmax (h) | AUCinf (ng·h/mL)1 | t1/2 (h) | |
|---|---|---|---|---|---|
| Methylphenidate hydrochloride extended-release tablets 36 mg | 10 | 9.9 ± 5.5 | 7.0 ± 2.1 | 112 ± 55.9 | 4.3 ± 2.0 |
| Methylphenidate hydrochloride extended-release tablets 54 mg | 8 | 12.8 ± 3.4 | 6.8 ± 1.7 | 141 ± 34.3 | 3.6 ± 0.5 |
| Methylphenidate hydrochloride extended-release tablets 72 mg | 6 | 17.8 ± 4.5 | 7.0 ± 1.8 | 186 ± 33.9 | 3.5 ± 0.5 |
- 1. Not recommended. In the clinical study, only 62 adolescents received methylphenidate hydrochloride extended-release tablets at this dose level.
Adults
The mean single dose pharmacokinetic parameters in 36 healthy adults following the administration of methylphenidate hydrochloride extended-release tablets 18 mg q.d. and methylphenidate hydrochloride 5 mg t.i.d. are summarized in Table 12.
Table 12: Pharmacokinetic Parameters in Adult Subjects after Single Dosing (Mean ± SD)
| Parameters | Methylphenidate Hydrochloride Extended-Release Tablets (18 mg q.d.) (n=36) | Methylphenidate Hydrochloride (5 mg t.i.d.) (n=35) |
| Cmax (ng/mL) | 3.7 ± 1.0 | 4.2 ± 1.0 |
| Parameters | Methylphenidate Hydrochloride Extended-Release Tablets (18 mg q.d.) (n=36) | Methylphenidate Hydrochloride (5 mg t.i.d.) (n=35) |
| Tmax (h) | 6.8 ± 1.8 | 6.5 ± 1.8 |
| AUCinf (ng·h/mL) | 41.8 ± 13.9 | 38.0 ± 11.0 |
| T½ (h) | 3.5 ± 0.4 | 3.0 ± 0.5 |
The mean single dose and steady-state pharmacokinetic parameters in 25 healthy adults following the administration of methylphenidate hydrochloride extended-release tablets 54 and 72 mg q.d. are summarized in Table 13.
Table 13: Summary of Methylphenidate Hydrochloride Extended-Release Tablets Pharmacokinetic Parameters in Adult Subjects Following Single Dose and at Steady-State (Mean ± SD)
| n | Cmax (ng/mL) | Tmax (h)1 | AUCinf (ng·h/mL) | t1/2 (h) | ||||
|---|---|---|---|---|---|---|---|---|
| Single Dose | ||||||||
Methylphenidate Hydrochloride Extended-Release Tablets 54 mg | 25 | 12.03 ± 3.54 | 6 (1-10) | 130 ± 32.4 | 3.58 ± 0.629 | |||
Methylphenidate Hydrochloride Extended-Release Tablets 72 mg | 25 | 17.12 ± 5.80 | 6 (5-10) | 196 ± 65.7 | 3.57 ± 0.617 | |||
| Steady State | ||||||||
Methylphenidate Hydrochloride Extended-Release Tablets 54 mg | 25 | 12.45 ± 2.84 | 6 (1-10) | 139 ± 33.62, 3 | 3.60 ± 0.844 | |||
Methylphenidate Hydrochloride Extended-Release Tablets 72 mg | 25 | 16.12 ± 4.60 | 6 (5-8) | 185 ± 49.03 | 3.63 ± 0.49 | |||
- 1. median and range are listed
- 2. n=24
- 3. AUCtau
Distribution:
Plasma methylphenidate concentrations in adults decline bi-exponentially following oral administration. The half-life of methylphenidate in adults following oral administration of methylphenidate hydrochloride extended-release tablets was approximately 3.5 h. In humans, 15 ± 5% of methylphenidate in the blood is bound to plasma proteins.
Metabolism:
In humans, methylphenidate is metabolized primarily by de- esterification to PPAA, which has little pharmacologic activity. In adults the metabolism of methylphenidate hydrochloride extended-release tablets q.d., as evaluated by metabolism to PPAA, is similar to that of methylphenidate t.i.d. The metabolism of single and repeated q.d. doses of methylphenidate hydrochloride extended-release tablets is similar.
Elimination:
After oral dosing of radio-labelled methylphenidate in humans, about 90% of the radioactivity was recovered in urine. The main urinary metabolite was PPAA, accounting for approximately 80% of the dose (see 10.3 Pharmacokinetics, Renal Insufficiency).
Dose Proportionality:
Following administration of methylphenidate hydrochloride extended-release tablets in single doses of 18, 36, and 54 mg/day to healthy adults, Cmax and AUCinf of d-methylphenidate were proportional to dose, whereas l-methylphenidate Cmax and AUCinf increased disproportionately with respect to dose. Following administration of methylphenidate hydrochloride extended-release tablets, plasma concentrations of the l-isomer were approximately 1/40th the plasma concentrations of the d-isomer.
In a multiple-dose study in adolescent ADHD patients aged 13 to 16 administered their prescribed dose (18 to 72 mg/day) of methylphenidate hydrochloride extended-release tablets, mean Cmax and AUC during a dosing interval of the d- isomer and total methylphenidate increased proportionally with respect to dose.
Food Effects:
In patients, there were no differences in either the pharmacokinetics or the pharmacodynamic performance of methylphenidate hydrochloride extended-release tablets when administered after a high-fat breakfast. There is no evidence of dose dumping in the presence or absence of food.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of methylphenidate hydrochloride extended-release tablets have not been studied in children less than 6 years of age, and methylphenidate Hydrochloride extended release tablets should not be used in this patient population.
Geriatrics: There are no data available for the use of methylphenidate hydrochloride
- -release tablets in patients over 65 years of age.
- Sex: In healthy adults, the mean dose-adjusted AUCinf values for methylphenidate hydrochloride extended-release tablets were 36.7 ng·h/mL in men and 37.1 ng·h/mL in women, with no differences noted between the two groups.
- Pregnancy and Breast-feeding: A study conducted in rats indicated that the distribution profiles of methylphenidate in milk and plasma are similar. Methylphenidate has been detected in human milk. Based on breast milk sampling from five mothers, methylphenidate concentrations in human milk resulted in infant doses of 0.16% to 0.7% of the maternal weight adjusted dosage, and a milk to maternal plasma ratio ranging between 1.1 and 2.7.
- Ethnic Origin: In adults receiving methylphenidate hydrochloride extended-release tablets, dose-adjusted AUCinf was consistent across ethnic groups; however, the sample size may have been insufficient to detect ethnic variations in pharmacokinetics.
- Hepatic Insufficiency: Methylphenidate hydrochloride extended-release tablets has not been studied in patients with hepatic insufficiency.
- Renal Insufficiency: There is very limited experience with the use of methylphenidate in patients with renal insufficiency. Renal clearance is not significant for methylphenidate elimination, but the main methylphenidate metabolic product, PPAA, is predominantly (80%) cleared through the urine.
Non-Clinical Pharmacokinetics
Studies primarily in humans and rats, as well as limited information available for mice, dogs, monkeys and other species, demonstrate that methylphenidate is readily absorbed, distributed, metabolized and eliminated regardless of the route of administration. While the kinetic rates for these processes are similar among different species, there are differences in metabolic profiles. Distribution of metabolites differs from that of the unchanged parent material, with most of the material that reaches the brain consisting of the unchanged parent compound. Biotransformation in the gut or first-pass metabolism, or both, is common among the species studied. The primary metabolite in humans and a major metabolite in other species is alpha-phenyl-alpha-(2-piperidyl) acetic acid (PPAA), also commonly called ritalinic acid. Pharmacokinetic data showed dose-dependent exposure to methylphenidate and PPAA in adult animals; in juvenile rats, exposure was more than dose-proportional. In the presence of alcohol, an intermediate metabolite, ethylphenidate, is produced. The amount of ethylphenidate production is proportional to the blood alcohol concentration. Excretion of radioactivity into breast milk was observed after single oral administration of 5 mg/kg 14C-methylphenidate hydrochloride to lactating rats.
11 STORAGE, STABILITY AND DISPOSAL
Store 15°C to 30°C. Protect from moisture.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: methylphenidate hydrochloride USP
Chemical name: (RS)-Methyl-2-phenyl-2-[(RS)-piperidin-2-yl] acetate, hydrochloride
Molecular formula and molecular mass: C14H19NO2·HCl, 269.77 g/mol
Structural formula:
O H NH HOCH3 + O H NH HOCH3 H2 2HCl .
Physicochemical properties: methylphenidate hydrochloride USP is a white powder pH: methylphenidate hydrochloride solutions are acidic to litmus pKa: 8.9
Solubility: freely soluble in water and in methanol, soluble in alcohol, and slightly soluble in chloroform and in acetone
Melting Point: 224°C to 226°C
14 CLINICAL TRIALS
14.1 Clinical Trials by Indications
A diagnosis of ADHD (DSM-IV) implies the presence of hyperactive-impulsive or inattentive symptoms that caused impairment and that were present before age 7 years. The symptoms must be persistent, must be more severe than is typically observed in individuals at a comparable level of development, must cause clinically significant impairment, e.g., in social, academic, or occupational functioning, and must be present in 2 or more settings, e.g., school (or work) and at home. The symptoms must not be better accounted for by another mental disorder. For the Inattentive Type, at least 6 of the following symptoms must have persisted for at least 6 months: lack of attention to details/careless mistakes, lack of sustained attention, poor listener, failure to follow through on tasks, poor organization, avoids tasks requiring sustained mental effort, loses things, easily distracted, forgetful. For the Hyperactive-Impulsive Type, at least 6 of the following symptoms must have persisted for at least 6 months: fidgeting/squirming, leaving seat, inappropriate running/climbing, difficulty with quiet activities, “on the go,” excessive talking, blurting answers, can’t wait turn, intrusive. For a Combined Type diagnosis, both inattentive and hyperactive-impulsive criteria must be met.
Attention Deficit Hyperactivity Disorder in Children
Table 14: Summary of patient demographics for clinical trials in children with ADHD
| Study No. | Study Design | Methylphenidate Hydrochloride Extended-Release Tablets Dose/Treatment Duration | Study subjects (n) | Mean Age (years) [Range] | Primary Efficacy Variable |
| Study 1 | Double-blind, randomized, 3-period, 6-sequence crossover, placebo-controlled, comparative vs. IR methylphenidate | 18, 36 or 54 mg once daily | 64 | 9.2 [6-12] | IOWA Conners Rating scale for inattention/ overactivity |
| Study 2 | Double-blind, randomized, placebo-controlled, active- controlled, crossover, comparative vs. IR methylphenidate | 18, 36 or 54 mg once daily | 70 | 9.1 [6-12] | IOWA Conners Rating scale for inattention/ overactivity |
| Study 3 | Double-blind, randomized, placebo-controlled, active- controlled, parallel group vs. IR methylphenidate | 18, 36 or 54 mg once daily | 282 | 8.7 [6-12] | IOWA Conners Rating scale for inattention/ overactivity |
Methylphenidate hydrochloride extended-release tablets was demonstrated to be effective in the treatment of ADHD in three double-blind, active- and placebo-controlled studies involving in 416 children aged six to twelve who met the Diagnostic and Statistical Manual 4th edition (DSM-IV) criteria for ADHD. The controlled studies compared methylphenidate hydrochloride extended-release tablets q.d. (18, 36 or 54 mg), methylphenidate hydrochloride t.i.d. over 12 hours (15, 30 or 45 mg total daily dose), and placebo in two single-centre, 3-week, crossover studies (Study 1 and Study 2) and in a multicentre, 4-week, parallel-group comparison (Study 3). The primary comparison of interest in all three trials was methylphenidate hydrochloride extended-release tablets versus placebo.
Symptoms of ADHD were evaluated by community school teachers using the Inattention/Overactivity with Aggression (IOWA) Conners scale. Significant reduction in the Inattention/Overactivity subscale in the treatment group versus the placebo was shown consistently across all three controlled studies for methylphenidate hydrochloride extended-release tablets q.d. and methylphenidate hydrochloride t.i.d. (p < 0.001). The scores for the placebo-controlled parallel study for all three treatment groups are presented in Figure 2.
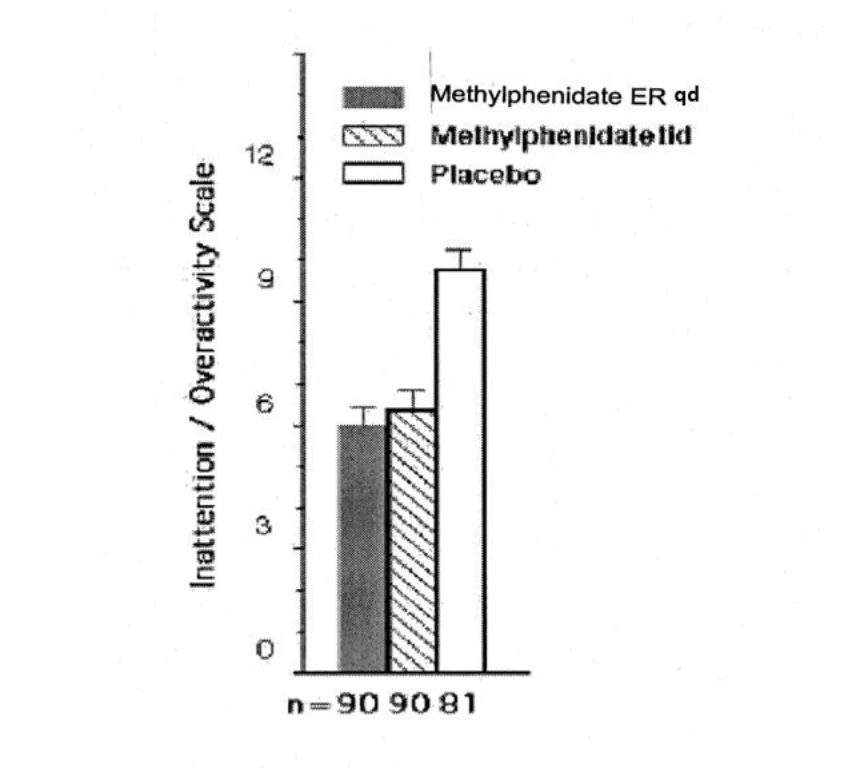
Figure 2: Mean community school teacher IOWA Conners Inattention/Overactivity scores with methylphenidate hydrochloride extended-release tablets q.d. (18, 36 or 54 mg), methylphenidate hydrochloride t.i.d. over 12 hours (15, 30 or 45 mg total daily dose), and placebo. The study involved 4 weeks of parallel-group treatments with a Last Observation Carried Forward analysis for weeks 2 to 4. Data at Week 4 is shown. Error bars represent mean plus standard error of the mean.
Studies 1 and 2
In the two placebo-controlled crossover studies (Studies 1 and 2), symptoms of ADHD were evaluated by laboratory school teachers using the SKAMP (Swanson, Kotkin, Agler, M-Flynn and Pelham) laboratory school rating scale. Significant improvement in attention and behaviour versus placebo was shown consistently across the two studies (p < 0.005). Efficacy was maintained through 12 hours after dosing, and the sustained beneficial effects of methylphenidate hydrochloride extended-release tablets q.d. therapy seen throughout the laboratory classroom day were comparable in duration to those with methylphenidate hydrochloride t.i.d. Figure 3 presents the laboratory school teacher SKAMP ratings for methylphenidate hydrochloride extended-release tablets q.d., methylphenidate hydrochloride t.i.d. and placebo in Study 1. Similar results were obtained in Study 2.
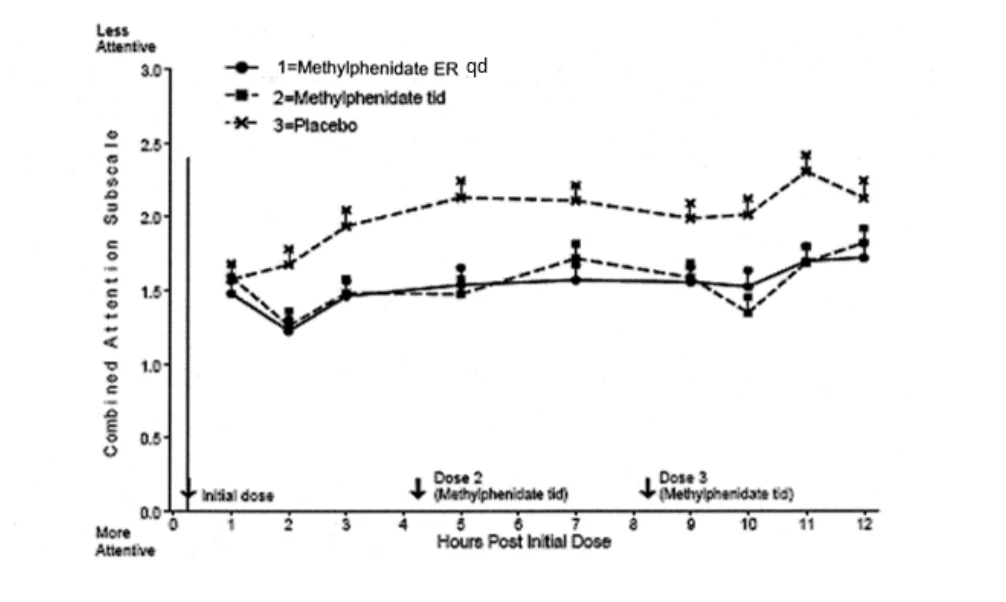
Figure 3: Mean laboratory school teacher SKAMP Ratings of Combined Attention (Study 1) with Methylphenidate Hydrochloride Extended-Release Tablets q.d. (18, 36 or 54 mg), methylphenidate hydrochloride t.i.d. over 12 hours (15, 30 or 45 mg total daily dose) and placebo. Error bars represent mean plus standard error of the mean. The sample sizes for Methylphenidate Hydrochloride Extended-Release Tablets, methylphenidate hydrochloride t.i.d., and placebo groups were 60, 62 and 60, respectively.
Attention Deficit Hyperactivity Disorder in Adolescents
Table 15: Summary of patient demographics for clinical trials in adolescents with ADHD
| Study No. | Study Design | Methylphenidate Hydrochloride Extended-Release Tablets Dose/Treatment Duration | Study subjects (n) | Mean Age (years) [Range] | Primary Efficacy Variable |
|---|---|---|---|---|---|
| Study 4 | Double-blind, randomized, placebo- | titration to 72 mg once daily | 220 | 14.7 [13-18] | Investigator ADHD rating scale |
| Study No. | Study Design | Methylphenidate Hydrochloride Extended-Release Tablets Dose/Treatment Duration | Study subjects (n) | Mean Age (years) [Range] | Primary Efficacy Variable |
|---|---|---|---|---|---|
| controlled | |||||
Study 4
In a randomized, double-blind, multicentre, placebo-controlled trial (Study 4) involving 177 adolescent patients aged 13 to 18 who met the DSM-IV criteria for ADHD, methylphenidate hydrochloride extended-release tablets was demonstrated to be effective in the treatment of ADHD and was well tolerated at doses up to 72 mg/day (1.4 mg/kg/day). Of 220 patients who entered an open 4-week titration phase, 177 were titrated to an individualized dose (maximum 72 mg/day) based on meeting specific improvement criteria on the ADHD Rating Scale and the Global Assessment of Effectiveness with acceptable tolerability. Patients who met these criteria were then randomized to receive either their individualized dose of methylphenidate hydrochloride extended-release tablets (18 to 72 mg/day, n = 87) or placebo (n = 90) during a two-week double-blind phase. At the end of this phase, mean scores for the investigator rating on the ADHD Rating Scale for methylphenidate hydrochloride extended-release tablets were significantly improved relative to placebo (CON –14.93; PLA –9.58; p=0.001). Mean scores for methylphenidate hydrochloride extended-release tablets and placebo, respectively, at the end of the double-blind phase were 16.62 and 21.40, compared to 31.55 and 30.99 at baseline.
Attention Deficit Hyperactivity Disorder in Adults
Table 16: Summary of patient demographics for clinical trials in adults with ADHD
| Study No. | Study Design | Methylphenidate Hydrochloride Extended-Release Tablets Dose/Treatment Duration | Study subjects (n) | Mean Age (years) [Range] | Primary Efficacy Variable |
|---|---|---|---|---|---|
| Study 5 | Double-blind, randomized, placebo-controlled, parallel group, dose-response | fixed doses of 18, 36 and 72 mg once daily | 401 | 34.0 [18-63] | Investigator-rated Connors Adult ADHD Rating Scale (CAARS) total score |
Study 5
In a 5-week, randomized, double-blind, multicentre, placebo-controlled, dose-response trial involving 401 adults aged 18 to 65 years who met the DSM-IV criteria for ADHD, methylphenidate hydrochloride extended-release tablets was demonstrated to be effective in the treatment of ADHD using once daily fixed doses of 18 mg, 36 mg and 72 mg. Efficacy was evaluated by the mean change from baseline to double-blind endpoint in the investigator-rated Connors' Adult ADHD Rating Scale (CAARS) total score. All doses of methylphenidate hydrochloride extended-release tablets (18 mg, 36 mg and 72 mg/day) were statistically significantly superior to placebo in improving the CAARS total scores at double-blind endpoint compared to baseline (mean change of -7.6 for placebo, -10.6 (p=0.0146) for methylphenidate hydrochloride extended-release tablets 18 mg, -11.5 (p=0.0131) for methylphenidate hydrochloride extended-release tablets 36 mg and -13.7 (p<0.0001) for the methylphenidate Hydrochloride extended release tablets 72 mg). Statistically significant differences compared to placebo were first observed at Week 1. Secondary endpoints included the investigator-rated Clinical Global Impressions - Severity (CGI-S) and the CAARS-S:S (patient-rated CAARS scale). The results from the secondary endpoints were consistent with the primary endpoint.
14.2 Comparative Bioavailability Studies
A randomized, two treatment, two period, single dose (1 x 18 mg), crossover bioequivalence study of APO-METHYLPHENIDATE ER (Apotex Inc.) and CONCERTA® (Janssen-Ortho Inc.) was conducted in healthy human adult subjects under fasting conditions. A summary of the data from the 23 subjects that were included in the statistical analysis are presented in the table below.
Summary Table of the Comparative Bioavailability Data
Methylphenidate (1 x 18 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 45.56 50.10 (53) | 46.40 51.34 (52) | 98.2 | 92.2 – 104.6 |
AUCI (ng·h/mL) | 48.03 53.03 (54) | 47.84 53.37 (55) | 100.4 | 94.5 – 106.7 |
Cmax (ng/mL) | 4.74 5.27 (54) | 5.16 5.49 (38) | 91.9 | 82.7 – 102.1 |
Tmax3 (h) | 5.00 (2.00 – 8.00) | 6.00 (5.00 – 9.05) | ||
| T1/24 | 4.57 (33) | 3.90 (19) | ||
Methylphenidate (1 x 18 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| (h) | ||||
1 APO-METHYLPHENIDATE ER (methylphenidate hydrochloride) extended-release tablets, 18 mg (Apotex Inc.)
2 CONCERTA® (methylphenidate hydrochloride) extended-release tablets, 18 mg (Janssen-Ortho Inc., Canada)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
A randomized, two treatment, two period, single dose (1 x 18 mg), crossover bioequivalence study of APO-METHYLPHENIDATE ER (Apotex Inc.) and CONCERTA® (Janssen-Ortho Inc.) was conducted in healthy human adult subjects under high-fat, high-calorie, fed conditions. A summary of the data from the 16 subjects that were included in the statistical analysis are presented in the table below.
Summary Table of the Comparative Bioavailability Data
Methylphenidate (1 x 18 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 50.70 53.18 (34) | 54.46 57.50 (34) | 93.1 | 88.1 – 98.4 |
AUCI (ng·h/mL) | 59.16 59.79 (34) | 55.70 58.92 (35) | 106.2 | 100.9 – 111.8 |
Cmax (ng/mL) | 5.26 5.47 (30) | 5.53 5.81 (33) | 95.0 | 90.3 – 100.0 |
Tmax3 (h) | 5.00 (2.00 – 9.00) | 7.00 (5.00 – 9.00) | ||
T1/24 (h) | 7.12 (63) | 3.48 (14) | ||
1 APO-METHYLPHENIDATE ER (methylphenidate hydrochloride) extended-release tablets, 18 mg (Apotex Inc.)
2 CONCERTA® (methylphenidate hydrochloride) extended-release tablets, 18 mg (Janssen-Ortho Inc., Canada)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
A randomized, two treatment, two period, single dose (1 x 54 mg), crossover bioequivalence study of APO-METHYLPHENIDATE ER (Apotex Inc.) and CONCERTA® (Janssen-Ortho Inc.) was conducted in healthy human adult subjects under fasting conditions. A summary of the data from the 17 subjects that were included in the statistical analysis are presented in the table below.
Summary Table of the Comparative Bioavailability Data
Methylphenidate (1 x 54 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 126.40 138.80 (49) | 126.97 139.66 (47) | 99.6 | 95.2 – 104.1 |
AUCI (ng·h/mL) | 130.25 140.82 (51) | 128.81 141.64 (47) | 101.1 | 97.3 – 105.1 |
Cmax (ng/mL) | 14.06 15.39 (48) | 12.14 13.19 (43) | 115.7 | 106.5 – 125.8 |
Tmax3 (h) | 5.00 (4.50 – 8.00) | 6.02 (1.00 – 8.00) | ||
T1/24 (h) | 4.27 (39) | 3.78 (11) | ||
1 APO-METHYLPHENIDATE ER (methylphenidate hydrochloride) extended-release tablets, 54 mg (Apotex Inc.)
2 CONCERTA® (methylphenidate hydrochloride) extended-release tablets, 54 mg (Janssen-Ortho Inc., Canada)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
A randomized, two treatment, two period, single dose (1 x 54 mg), crossover bioequivalence study of APO-METHYLPHENIDATE ER (Apotex Inc.) and CONCERTA® (Janssen-Ortho Inc.) was conducted in healthy human adult subjects under high-fat, high-calorie, fed conditions. A summary of the data from the 16 subjects that were included in the statistical analysis are presented in the table below.
Summary Table of the Comparative Bioavailability Data
Methylphenidate (1 x 54 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 159.58 165.37 (29) | 161.07 165.26 (28) | 99.1 | 94.1 – 104.4 |
Methylphenidate (1 x 54 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCI (ng·h/mL) | 162.91 168.99 (29) | 163.23 167.72 (29) | 99.8 | 94.9 – 105.0 |
Cmax (ng/mL) | 18.63 19.08 (23) | 15.74 16.03 (21) | 118.4 | 109.8 – 127.6 |
Tmax3 (h) | 5.00 (3.00 – 6.00) | 7.50 (5.00 – 11.00) | ||
T1/24 (h) | 4.75 (35) | 3.61 (18) | ||
1 APO-METHYLPHENIDATE ER (methylphenidate hydrochloride) extended-release tablets, 54 mg (Apotex Inc.)
2 CONCERTA® (methylphenidate hydrochloride) extended-release tablets, 54 mg (Janssen-Ortho Inc., Canada)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology: The toxicology program for methylphenidate and the oral controlled-release OROS methylphenidate dosage form consists of acute toxicity, long-term toxicity, carcinogenicity and mutagenicity, reproductive and developmental toxicity, and other special toxicity studies.
- Acute Toxicity
The acute toxicity of methylphenidate hydrochloride has been studied primarily in mice and rats, and additionally in rabbits and dogs. Published oral LD50 values for rodents and rabbits range from approximately 190 to 900 mg/kg. The probable cause of death in LD50 studies was excessive central adrenergic stimulation. Clinical signs noted with high doses of methylphenidate in animal acute toxicity studies include agitation and increased motor activity, tremors and convulsions, decreased food consumption and stereotypic behaviours such as licking or gnawing.
A dog study was conducted to study the abuse potential of methylphenidate hydrochloride extended-release tablets (N=8) and immediate release methylphenidate (N=8). The dogs were intravenously administered with pulverized methylphenidate hydrochloride extended-release tablets or methylphenidate tablets mixed with liquid. Death occurred after a single 0.5 mg or
1 mg/kg dose of methylphenidate hydrochloride extended-release tablets. Mortality was not observed in methylphenidate-treated dogs dosed at 1 mg/kg/day for 2 weeks. It is likely that the deaths were due the particles present in the pulverized methylphenidate hydrochloride extended-release tablets.
- Long-Term Toxicity
Treatment with methylphenidate hydrochloride at repeated high doses has demonstrated transient effects on body weight in rats and mice. The liver was the primary target organ for toxicity in mice and rats, with male mice being the most sensitive showing hepatocellular degeneration. Methylphenidate has shown some effects on maturation and estrous cyclicity in neonatal rats; estrous cycles were reversibly affected in older rats. Reversible effects of methylphenidate were seen on skeletal growth in neonatal rats; such effects were not seen in older rats. Endocrine effects of MPH have generally been inconsistent or did not show a dose response. The potential gastrointestinal (GI) effects and systemic toxicity of the OROS methylphenidate dosage form were evaluated in a study conducted in dogs. Except for excessive salivation, no other treatment-related clinical signs were observed. No treatment-related findings were seen in body or organ weights, physical exams, ophthalmic exams, qualitative food consumption, hematology, clinical chemistry, urinalysis, macroscopic exams or histopathologic evaluation of tissues. No treatment-related GI irritation or systemic effects were seen for oral doses up to 72 mg/day for 30 days.
A second study in beagle dogs was conducted to determine the possible local gastrointestinal and systemic effects of methylphenidate hydrochloride extended-release tablets after daily administration (0, 72, 144 or 216 mg/day) for 4 weeks. Females in all methylphenidate hydrochloride extended-release tablets groups showed toxicologic effects such as hyperactivity, reduced food consumption, and decreased mean body weight gain; in males similar effects were seen only in the two higher methylphenidate hydrochloride extended-release tablets groups (144 and 216 mg/day). However, with the exception of mean body weight gain in 216 mg/day females, the methylphenidate hydrochloride extended-release tablets -related changes resolved during recovery.
Genotoxicity: Methylphenidate was not mutagenic in the in vitro Ames reverse mutation assay or the in vitro mouse lymphoma cell forward mutation assay. Sister chromatid exchanges and chromosome aberrations were increased, indicative of a weak clastogenic response, in an in vitro assay in cultured Chinese Hamster Ovary cells. Methylphenidate was negative in vivo in males and females in the mouse bone marrow micronucleus assay.
Carcinogenicity: In a lifetime carcinogenicity study carried out in B6C3F1 mice, methylphenidate hydrochloride caused an increase in hepatocellular adenomas and, in males only, an increase in hepatoblastomas at a daily dose of approximately 60 mg/kg/day. This dose is approximately 30 times and 4 times the maximum recommended human dose of methylphenidate hydrochloride extended-release tablets on a mg/kg and mg/m2 basis, respectively. Hepatoblastoma is a relatively rare rodent malignant tumour type. There was no increase in total malignant hepatic tumours. The mouse strain used is sensitive to the development of hepatic tumours, and the significance of these results to humans is unknown.
Methylphenidate hydrochloride did not cause any increases in tumours in a lifetime carcinogenicity study carried out in F344 rats; the highest dose used was approximately 45 mg/kg/day, which is approximately 22 times and 5 times the maximum recommended human dose of methylphenidate hydrochloride extended-release tablets on a mg/kg and mg/m2 basis, respectively.
In a 24-week carcinogenicity study in the transgenic mouse strain p53+/-, which is sensitive to genotoxic carcinogens, there was no evidence of carcinogenicity. Male and female mice were fed diets containing the same concentration of methylphenidate as in the lifetime carcinogenicity study; the high-dose groups were exposed to 60 to 74 mg/kg/day of methylphenidate hydrochloride.
Reproductive and Developmental Toxicology: Studies have been conducted in mice, rats and rabbits to evaluate the potential reproductive and developmental toxicity of methylphenidate. Rats appear to be a better animal model than rabbits for developmental/reproductive studies of methylphenidate, based on plasma AUC ratios of drug:metabolite.
Reproductive toxicity was studied using a Reproductive Assessment by Continuous Breeding (RACB) protocol or Sperm Morphology Vaginal Cytology Evaluations (SMVCE) endpoints to assess male and female reproductive functions. Methylphenidate hydrochloride did not impair fertility in male or female mice that were fed diets containing the drug in an 18-week Continuous Breeding study. The study was conducted at doses up to 160 mg/kg/day, approximately 80-fold and 8-fold the highest recommended human dose of methylphenidate hydrochloride extended-release tablets on a mg/kg and mg/m2 basis, respectively. A perinatal and postnatal development study with neurobehavioural assessments in rats indicated slight developmental delay and marginal alterations in neuromotor performance in offspring of the high-dose dams treated with 30 mg/kg/day methylphenidate hydrochloride (approximately 15 and 3 times the maximum recommended daily human dose for methylphenidate hydrochloride extended-release tablets [54 mg methylphenidate hydrochloride] on a mg/kg and mg/m2 basis, respectively). No effects on learning and memory were seen in offspring and no adverse effects were noted in offspring of dams treated with methylphenidate hydrochloride doses of 12.5 mg/kg/day and lower.
A teratology study conducted in rats supports the conclusion that methylphenidate is not a developmental toxicant at the dose levels tested, up to 30 mg/kg/day. The maternal no-observed-adverse-effect level (NOAEL) of methylphenidate hydrochloride was 5 mg/kg/day. No adverse effects on embryo/fetal viability, growth or malformations were seen. The developmental toxicity NOAEL of methylphenidate hydrochloride was at least 30 mg/kg/day. In a study conducted in rabbits, methylphenidate hydrochloride was shown to have teratogenic effects when given in doses of 200 mg/kg/day, which is approximately 100 times and 40 times the maximum recommended human dose on a mg/kg and mg/m2 basis, respectively.
Weaning juvenile rats (F0) of both sexes were administered methylphenidate hydrochloride at total daily doses of 5, 12.5, and 30 mg/kg for approximately 4.5 months. The no observed adverse effect level (NOAEL) for F0 juvenile toxicity was considered to be 12.5 mg/kg/day for males and 30 mg/kg/day for females. For F1 developmental toxicity the NOAEL was considered to be 12.5 mg/kg/day.
Special Toxicology: Five system transit and drug release studies conducted with the OROS methylphenidate dosage form in dogs showed no unexpected clinical signs during transit through the gastrointestinal (GI) tract. Membrane shells remained intact during GI transit with cumulative release of active ingredient generally comparable in vitro and in vivo.
Cellular toxicity profile of methylphenidate and effects of methylphenidate on mitochondrial function were evaluated in vitro using an MTT(3-[4,5-dimethythiazole-2-yl]-2,5-di-phenyl- tetrazolium bromide) assay. Results demonstrated that MPH in cell culture medium, at approximate concentrations of 0.125 and 0.25 mg/mL, was noncytotoxic to L-929 mouse fibroblast cells.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. CONCERTA® (methylphenidate hydrochloride extended-release tablets, 18 mg, 27 mg, 36 mg, and 54 mg), submission control 286261, Product Monograph, Janssen Inc. (SEP 24, 2024)