


Product Monograph - Apo-Pramipexole
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Driving and Operating Machinery | 08/2024 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Psychiatric | 08/2024 |
| 7 WARNINGS AND PRECAUTIONS, Neurologic | 08/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations .......................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ...................................................... 5
4.4 Administration ...................................................................................................... 8
4.5 Missed Dose .......................................................................................................... 8
5 OVERDOSAGE .............................................................................................................. 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 9
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
7.1 Special Populations ............................................................................................. 16
7.1.1 Pregnant Women ................................................................................................ 16
7.1.2 Breast-feeding .................................................................................................... 16
7.1.3 Pediatrics ............................................................................................................ 16
7.1.4 Geriatrics ............................................................................................................ 16
8 ADVERSE REACTIONS ................................................................................................ 17
8.1 Adverse Reaction Overview ................................................................................ 17
8.2 Clinical Trial Adverse Reactions........................................................................... 18
8.3 Less Common Clinical Trial Adverse Reactions.................................................... 24
8.5 Post-Market Adverse Reactions .......................................................................... 27
9 DRUG INTERACTIONS ................................................................................................ 28
9.2 Drug Interactions Overview ................................................................................ 28
9.3 Drug-Behavioural Interactions ............................................................................ 29
9.4 Drug-Drug Interactions ....................................................................................... 29
9.5 Drug-Food Interactions ....................................................................................... 32
9.6 Drug-Herb Interactions ....................................................................................... 32
9.7 Drug-Laboratory Test Interactions ...................................................................... 32
10 CLINICAL PHARMACOLOGY ....................................................................................... 32
10.1 Mechanism of Action .......................................................................................... 32
10.2 Pharmacodynamics ............................................................................................. 32
10.3 Pharmacokinetics ................................................................................................ 35
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 37
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 37
PART II: SCIENTIFIC INFORMATION ....................................................................................... 38
13 PHARMACEUTICAL INFORMATION ............................................................................ 38
14 CLINICAL TRIALS ........................................................................................................ 39
14.1 Clinical Trials by Indication .................................................................................. 39
14.2 Comparative Bioavailability Studies .................................................................... 46
16 NON-CLINICAL TOXICOLOGY ...................................................................................... 47
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 63
PATIENT MEDICATION INFORMATION .................................................................................. 64
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) is indicated for adults, as:
- treatment of the signs and symptoms of idiopathic Parkinson’s disease. APO-PRAMIPEXOLE may be used both as early therapy, without concomitant levodopa, and as an adjunct to levodopa.
- symptomatic treatment of moderate to severe idiopathic Restless Legs Syndrome. The effectiveness of APO-PRAMIPEXOLE used for longer than 12 weeks has not been systematically evaluated in controlled trials for Restless Legs Syndrome. The physician who elects to prescribe APO-PRAMIPEXOLE for an extended time should periodically re-evaluate the long-term usefulness for the individual patient.
1.1 Pediatrics
Pediatrics (< 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): The majority of pramipexole (88%) is cleared via renal secretion. Due to age-related reduction in renal function, the elderly have a slower clearance of pramipexole (approximately 25 to 30% lower). The efficacy and safety appear to be unaffected, except the relative risk of hallucination is higher (see 7 WARNINGS AND PRECAUTIONS, 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) is contraindicated in patients who have demonstrated hypersensitivity to pramipexole or the excipients of the drug product (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Sudden Onset of Sleep and Somnolence Patients receiving treatment with APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) and other dopaminergic agents have reported suddenly falling asleep while engaged in activities of daily living, including operating a motor vehicle, which sometimes resulted in accidents. Although some of the patients reported somnolence while on APO-PRAMIPEXOLE, others perceived that they had no warning signs, such as excessive |
|---|
drowsiness, and believed that they were alert immediately prior to the event. Physicians should alert patients of the reported cases of sudden onset of sleep, bearing in mind that these events are NOT limited to initiation of therapy. Patients should also be advised that sudden onset of sleep has occurred without warning signs. If drowsiness or sudden onset of sleep should occur, patients should immediately contact their physician. Until further information is available on the management of this unpredictable and serious adverse event, patients should be warned not to drive or engage in other activities where impaired alertness could put themselves and others at risk of serious injury or death (e.g., operating machines). Substituting other dopamine agonists may not alleviate these symptoms, as episodes of falling asleep while engaged in activities of daily living have also been reported in patients taking these products. While dose reduction clearly reduces the degree of somnolence, there is insufficient information to establish that dose reduction will eliminate episodes of falling asleep while engaged in activities of daily living. Presently, the precise cause of this event is unknown. It is known that many Parkinson’s disease patients experience alterations in sleep architecture, which results in excessive daytime sleepiness or spontaneous dozing, and that dopaminergic agents can also induce sleepiness. |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
In all clinical studies, dosage was initiated at a subtherapeutic level to avoid orthostatic hypotension and severe adverse effects. APO-PRAMIPEXOLE should be titrated gradually in all patients. The dosage should be increased to achieve maximal therapeutic effect, balanced against the principal adverse reactions of dyskinesia, nausea, dizziness and hallucinations.
4.2 Recommended Dose and Dosage Adjustment
Parkinson’s Disease
The maximal recommended dose of APO-PRAMIPEXOLE is 4.5 mg per day. APO-PRAMIPEXOLE is not recommended at the 6 mg per day dose since the incidence of some adverse reactions is higher.
Initial treatment
Dosages should be increased gradually from a starting dose of 0.375 mg/day given in three divided doses and should not be increased more frequently than every 5 to 7 days. A suggested ascending dosage schedule that was used in clinical studies is shown in the following table:
Table 1: ASCENDING-DOSE SCHEDULE OF APO-PRAMIPEXOLE
| Week | Dosage (mg) tid | Total Daily Dose (mg) |
| 1 | 0.125 | 0.375 |
| 2 | 0.25 | 0.75 |
| 3 | 0.50 | 1.5 |
| 4 | 0.75 | 2.25 |
| 5 | 1.00 | 3.0 |
| 6 | 1.25 | 3.75 |
| 7 | 1.50 | 4.5 |
*tid – three times a day
Maintenance treatment
Pramipexole dihydrochloride monohydrate tablets was effective and well-tolerated over a dosage range of 1.5 to 4.5 mg/day, administered in equally divided doses three times per day, as monotherapy or in combination with levodopa (approximately 800 mg/day). In a fixed-dose study in patients with early Parkinson’s disease, pramipexole dihydrochloride monohydrate tablets at doses of 3, 4.5 and 6 mg/day was not shown to provide any significant benefit beyond that achieved at a daily dose of 1.5 mg/day. For individual patients who have not achieved efficacy at 1.5 mg/day, higher doses can result in additional therapeutic benefit.
Discontinuation of Treatment
APO-PRAMIPEXOLE tablets should be tapered off at a rate of 0.75 mg per day until the daily dose has been reduced to 0.75 mg. Thereafter the dose should be reduced by 0.375 mg per day. Prior to tapering or discontinuation, patients should be informed about potential withdrawal symptoms and closely monitored thereafter (see 7 WARNINGS AND PRECAUTIONS, Neurologic, Dopamine Agonist Withdrawal Syndrome, and Neuroleptic Malignant Syndrome).
Dosing in patients with concomitant levodopa therapy
In patients with concomitant levodopa therapy it is recommended that the dosage of levodopa is reduced during both dose escalation and maintenance treatments with APO-PRAMIPEXOLE. In the controlled study in advanced Parkinson’s disease, the dosage of levodopa was reduced by an average of 27% from baseline. This may be necessary in order to avoid excessive dopaminergic stimulation.
Patients with renal impairment
Since the clearance of APO-PRAMIPEXOLE is reduced in patients with renal impairment (see 10.3 Pharmacokinetics, Renal Insufficiency), the following dosage recommendation should be considered:
Patients with a creatinine clearance above 50 mL/min require no reduction in daily dose or dosing frequency.
In patients with a creatinine clearance between 30 and 50 mL/min, the initial daily dose of APO-PRAMIPEXOLE should be administered in two divided doses, starting at 0.125 mg twice a day (0.25 mg daily). A maximum daily dose of 2.25 mg pramipexole should not be exceeded.
In patients with a creatinine clearance between 15 and 30 mL/min, the daily dose of APO-PRAMIPEXOLE should be administered in a single dose, starting at 0.125 mg daily. A maximum daily dose of 1.5 mg pramipexole should not be exceeded.
Pramipexole has not been adequately studied in patients with very severe renal impairment (creatinine Cl < 15 mL/min and hemodialysis patients) and its administration to patients with end stage renal disease is not recommended.
If renal function declines during maintenance therapy reduce APO-PRAMIPEXOLE daily dose by same percentage as decline in creatinine clearance, i.e., if creatinine clearance declines by 30%, then reduce APO-PRAMIPEXOLE daily dose by 30%. The daily dose can be administered in two divided doses if creatinine clearance is between 20 and 50 mL/min and as a single daily dose if creatinine clearance is less than 20 mL/min.
Patients with hepatic impairment
Dose reduction not considered necessary.
Restless Legs Syndrome (RLS)
Initial treatment
The recommended starting dose of APO-PRAMIPEXOLE is 0.125 mg taken once daily 2 to 3 hours before bedtime. For patients requiring additional symptomatic relief, the dose may be increased every 4 to 7 days to reach 0.50 mg per day (as shown in the table below):
Table 2: Ascending-Dose Schedule of APO-PRAMIPEXOLE
| Titration Step | Once Daily Evening Dose (mg) |
|---|---|
| 1 | 0.125 |
| 2* | 0.25 |
| 3* | 0.50 |
*if needed
Some patients may find optimal relief at 0.75 mg per day, albeit with a higher rate of adverse reactions. Intermediate doses (such as 0.375 mg or 0.625 mg per day) may be used. Prior to treatment, patients should be informed that augmentation may occur (see 7 WARNINGS AND PRECAUTIONS, Augmentation and Rebound in Restless Legs Syndrome). Patients should be re-assessed periodically, and the dose adjusted accordingly.
Treatment discontinuation
Due to the chronic and fluctuating nature of restless legs syndrome (RLS), continuous treatment may not be necessary. If discontinuation is desirable, tapering in 4 to 7 day intervals is recommended whenever possible. Prior to tapering or discontinuation, patients should be informed about potential withdrawal symptoms and closely monitored thereafter (see 7 WARNINGS AND PRECAUTIONS, Dopamine Agonist Withdrawal Syndrome, Neuroleptic Malignant Syndrome, and 8.5 Post-market adverse reactions).
In a 26 week placebo controlled clinical trial, rebound of RLS symptoms (worsening of symptom severity as compared to baseline) was observed in 10% of patients (14 out of 135) after abrupt discontinuation of pramipexole. This effect was found to be similar across all doses (0.125 mg to 0.75 mg).
Dosing in patients with renal impairment
The duration between up titration steps should be increased to 14 days in RLS patients with severe and moderately severe renal impairment (creatinine clearance 20 to 60 mL / min). See (10.3 Pharmacokinetics, Renal Insufficiency).
Dosing in patients with hepatic impairment
Dose reduction is not considered necessary in patients with hepatic impairment, as approx. 90% of absorbed drug is excreted through the kidneys.
Dosing in children and adolescents
Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics)
4.4 Administration
Parkinson’s Disease
APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) should be taken orally, swallowed with water, three times daily. The tablets can be taken with or without food.
Restless Legs Syndrome (RLS)
The tablets should be taken orally, swallowed with water, and can be taken either with or without food.
4.5 Missed Dose
Patients should be advised that if a dose is missed, they should not take a double dose, but continue with the regular treatment schedule.
5 OVERDOSAGE
Signs and Symptoms
There is no clinical experience with overdosage. The expected adverse events are those related to the pharmacodynamic profile of a dopamine agonist including nausea, vomiting, hyperkinesia, hallucinations, agitation and hypotension.
One patient with a 10-year history of schizophrenia (who participated in a schizophrenia study) took 11 mg/day of pramipexole dihydrochloride monohydrate tablets for two days; this was two to three times the daily dose recommended in the protocol. No adverse events were reported related to the increased dose. The blood pressure remained stable although pulse rates increased to between 100 and 120 beats/minute. The patient withdrew from the study at the end of week 2 due to lack of efficacy.
Recommended Management
There is no known antidote for overdosage of a dopamine agonist. If signs of central nervous system stimulation are present, a phenothiazine or other butyrophenone neuroleptic agent may be indicated; the efficacy of such drugs in reversing the effects of overdosage has not been assessed. Management of the overdose may require general supportive measures along with gastric lavage, intravenous fluids, and electrocardiogram monitoring.
Hemodialysis has not been shown to be helpful.
| For management of a suspected drug overdose, contact your regional Poison Control Centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Tablets 0.125 mg, 0.25 mg, 0.5 mg, 0.75 mg, 1.0 mg and 1.5 mg | Magnesium stearate, microcrystalline cellulose and starch (corn). |
Description
APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) are available in bottles of 100 tablets.
0.125 mg: White to off-white, round, flat-faced, beveled edge tablet. Engraved “APO” on one side, and “PR” over “.125” on the other side containing 0.125 mg pramipexole dihydrochloride monohydrate.
0.25 mg: White to off-white, oval, flat-faced, beveled edge tablet, engraved “APO” on one side and “PR” score “.25” on the other side containing 0.25 mg pramipexole dihydrochloride monohydrate.
0.5 mg: White to off-white, oval, flat-faced, beveled edge tablet, engraved “APO” on one side and “PR” score “.5” on the other side containing 0.5 mg pramipexole dihydrochloride monohydrate.
0.75 mg: White to off-white, oval, flat-faced, beveled edge tablet. Engraved “APO” on one side, and “PR.75” on the other side containing 0.75 mg pramipexole dihydrochloride monohydrate.
1.0 mg: White to off-white, round, flat-faced, beveled edge tablet, engraved “APO” on one side and “PR” over score “1” on the other side containing 1 mg pramipexole dihydrochloride monohydrate.
1.5 mg: White to off-white, round, flat-faced, beveled edge tablet, engraved “APO” on one side and “PR” over score “1.5” on the other side containing 1.5 mg pramipexole dihydrochloride monohydrate.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Fibrotic Complications
Although not reported with pramipexole in the clinical development program, cases of retroperitoneal fibrosis, pulmonary infiltrates, pleural effusion, pleural thickening, pericarditis, and cardiac valvulopathy have been reported in some patients treated with ergot-derived dopaminergic agents. While these complications may resolve when the drug is discontinued, complete resolution does not always occur.
Although these adverse events are believed to be related to the ergoline structure of these compounds, whether other, non ergot derived dopamine agonists can cause them is unknown.
A small number of reports have been received of possible fibrotic complications, including peritoneal fibrosis, pleural fibrosis, and pulmonary fibrosis, in the postmarketing experience for pramipexole dihydrochloride monohydrate tablets. While the evidence is not sufficient to establish a causal relationship between pramipexole dihydrochloride monohydrate tablets and these fibrotic complications, a contribution of pramipexole dihydrochloride monohydrate tablets cannot be completely ruled out in rare cases.
Carcinogenesis and Mutagenesis
For animal data, see 16 NON-CLINICAL TOXICOLOGY
Cardiovascular
Postural (orthostatic) Hypotension
In case of severe cardiovascular disease, care should be taken. Dopamine agonists appear to impair the systemic regulation of blood pressure with resulting postural (orthostatic) hypotension, especially during dose escalation. Postural (orthostatic) hypotension has been observed in patients treated with pramipexole dihydrochloride monohydrate tablets. Therefore, patients should be carefully monitored for signs and symptoms of orthostatic hypotension especially during dose escalation (see 4 DOSAGE AND ADMINISTRATION) and should be informed of this risk (see PATIENT MEDICATION INFORMATION).
In clinical trials of pramipexole dihydrochloride monohydrate tablets, however, and despite clear orthostatic effects in normal volunteers, the reported incidence of clinically significant orthostatic hypotension was not greater among those assigned to pramipexole dihydrochloride monohydrate tablets than among those assigned to placebo. This result is clearly unexpected in light of the previous experience with the risks of dopamine agonist therapy.
While this finding could reflect a unique property of pramipexole dihydrochloride monohydrate tablets, it might also be explained by the conditions of the study and the nature of the population enrolled in the clinical trials. Patients were very carefully titrated, and patients with active cardiovascular disease or significant orthostatic hypotension at baseline were excluded.
Dependence/Tolerance
Pramipexole dihydrochloride monohydrate tablets has not been systematically studied in animals or humans for its potential for abuse, tolerance, or physical dependence. However, in a rat model on cocaine self-administration, pramipexole dihydrochloride monohydrate tablets had little or no effect.
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery as somnolence or hallucinations can occur (see 3 SERIOUS WARNINGS AND PRECAUTION BOX, 7 WARNINGS AND PRECAUTIONS, Hallucinations and psychotic-like behaviour and Neurologic).
Monitoring and Laboratory Tests
There are no specific laboratory tests recommended for the management of patients receiving APO-PRAMIPEXOLE.
Musculoskeletal
Rhabdomyolysis
A single case of rhabdomyolysis occurred in a 49-year old male with advanced Parkinson’s disease treated with pramipexole dihydrochloride monohydrate tablets. The patient was hospitalized with an elevated CPK (10.631 IU/L). The symptoms resolved with discontinuation of the medication.
Neurologic
Augmentation and Rebound in Restless Legs Syndrome
Reports in the literature indicate treatment of Restless Legs Syndrome (RLS) with dopaminergic medications can result in augmentation. Augmentation refers to the earlier onset of symptoms in the evening (or even the afternoon), increased intensity of symptoms, and spread of symptoms to involve other extremities. A paradoxical response to treatment, where an increase in severity of symptoms with increasing dose of medication, can also be observed. Treatment of RLS with dopaminergic medications can result in a worsening of symptoms in the early morning hours, referred to as rebound. Rebound of RLS symptoms has been also observed as end-of-treatment rebound, i.e., worsening of symptoms following treatment cessation to a greater severity compared to baseline (before start of treatment).
Treatment with APO-PRAMIPEXOLE should be started with the recommended dose of 0.125 mg and may only be increased to reach a dose of 0.5 mg, if additional symptom relief is required. A daily dose of 0.75 mg should not be exceeded (see 4.2 Recommended Dose and Dosage Adjustment, Restless Legs Syndrome). Prior to treatment, patients should be informed that augmentation may occur. They should be regularly monitored for the occurrence of augmentation. If augmentation occurs, the adequacy of pramipexole treatment should be reviewed and dosage adjustment or discontinuation considered.
In RLS clinical trials, worsening of the RLS symptoms beyond baseline was reported for 10% of patients following abrupt discontinuation of pramipexole dihydrochloride monohydrate tablets treatment. The worsening of symptoms was independent of the pramipexole dihydrochloride monohydrate tablets dosage and generally resolved within one week. Tapering is recommended whenever possible if discontinuation is necessary (see 8.2 Clinical Trial Adverse Reactions).
Dopamine Agonist Withdrawal Syndrome (DAWS)
A drug withdrawal syndrome has been reported during tapering or after discontinuation of dopamine agonists including pramipexole. Limited data suggest that patients with impulse control disorders and those receiving high daily dose and/or high cumulative doses of dopamine agonists may be at higher risk for developing DAWS. Withdrawal symptoms do not respond to levodopa, and may include apathy, anxiety, depression, fatigue, sweating, panic attacks, insomnia, irritability and pain. The syndrome has been reported in patients who did or did not develop impulse control disorders during treatment with pramipexole dihydrochloride monohydrate tablets. Prior to discontinuation, patients should be informed about potential withdrawal symptoms, and closely monitored during tapering and after discontinuation. In case of severe withdrawal symptoms, temporary re-administration of APO-PRAMIPEXOLE at the lowest effective dose to manage these symptoms may be considered (see 4.2 Recommended Dose and Dosage Adjustment, discontinuation of treatment).
Dyskinesia
APO-PRAMIPEXOLE may potentiate the dopaminergic side effects of levodopa and may cause or exacerbate pre-existing dyskinesia. Decreasing the dose of levodopa may ameliorate this side effect.
Dystonia
Patients with Parkinson’s disease may present with axial dystonia such as antecollis, camptocormia or pleurothotonus (Pisa Syndrome). Dystonia has occasionally been reported following initiation of dopamine agonists including pramipexole and may also occur several months following medication initiation or adjustment. If dystonia occurs, the dopaminergic medication regimen should be reviewed and an adjustment considered.
Neuroleptic Malignant Syndrome
A symptom complex resembling the neuroleptic malignant syndrome (characterized by elevated temperature, muscular rigidity, altered consciousness, and autonomic instability), with no other obvious etiology, has been reported in association with rapid dose reduction, withdrawal of, or changes in anti-Parkinsonian therapy, including pramipexole dihydrochloride monohydrate tablets (see 4.2 Recommended Dose and Dosage Adjustment, discontinuation of treatment).
Ophthalmologic
Retinal Pathology in Albino Rats
Pathologic changes (degeneration and loss of photoreceptor cells) were observed in the retina of albino rats in the 2-year carcinogenicity study with pramipexole.
The albino rats seem to be more susceptible than pigmented rats to the damaging effect of pramipexole and light. While the potential significance of this effect on humans has not been established, it cannot be excluded that human albinos (or people who suffer from albinismus oculi) might have an increased susceptibility to pramipexole compared to normally pigmented people. Therefore, such patients should take APO-PRAMIPEXOLE only under ophthalmological monitoring (see 16 NON-CLINICAL TOXICOLOGY, Retinopathy In Albino Rats).
Psychiatric
Impulse Control Disorders and Compulsive Behaviors
Patients and caregivers should be made aware that abnormal behaviour (reflecting symptoms of impulse control disorders and compulsive behaviours) such as pathological gambling, increased libido, hypersexuality, binge eating, or compulsive shopping, and/or other intense urges and the inability to control these urges, have been reported in patients treated with dopaminergic drugs. Because patients may not recognize these behaviours as abnormal, it is important for physicians to specifically ask patients and caregivers to identify new behaviour patterns. Dose reduction/tapered discontinuation should be considered, and be performed by the treating physician in close collaboration with the patient and caregiver, based on the patient’s response and potential withdrawal symptoms (see 7 WARNINGS AND PRECAUTIONS, Dopamine Agonist Withdrawal Syndrome).
Dopamine Dysregulation Syndrome (DDS)
Dopamine dysregulation syndrome (DDS) has been observed in some patients treated with pramipexole dihydrochloride monohydrate tablets. This is an addictive disorder that leads to the overuse of dopaminergic medicines. Patients and caregivers must be warned of the potential risk of developing DDS before starting treatment.
Hallucinations and psychotic-like behavior
Hallucinations and confusion are known side effects of treatment with dopamine agonists and levodopa. Hallucinations were more frequent when pramipexole dihydrochloride monohydrate tablets was given in combination with levodopa in patients with advanced disease than in monotherapy in patients with early disease. Patients should be aware of the fact that hallucinations (mostly visual) and psychotic-like behavior can occur (see 8.5 Post-Market Adverse Reactions).
In the double-blind, placebo-controlled trials in early Parkinson’s disease, hallucinations were observed in 9% (35 of 388) of patients receiving pramipexole dihydrochloride monohydrate tablets, compared with 2.6% (6 of 235) of patients receiving placebo. In the double-blind, placebo-controlled trials in advanced Parkinson’s disease, where patients received pramipexole dihydrochloride monohydrate tablets and concomitant levodopa, hallucinations were observed in 16.5% (43 of 260) of patients receiving pramipexole dihydrochloride monohydrate tablets compared with 3.8% (10 of 264) of patients receiving placebo. Hallucinations were of sufficient severity to cause discontinuation of treatment in 3.1% of the early Parkinson’s disease patients and 2.7% of the advanced Parkinson’s disease patients compared with about 0.4% of placebo patients in both populations.
Age appears to increase the risk of hallucinations. In patients with early Parkinson’s disease, the risk of hallucinations was 1.9 times and 6.8 times greater in pramipexole dihydrochloride monohydrate tablets patients than placebo patients <65 years old, and >65 years old, respectively. In patients with advanced Parkinson’s disease, the risk of hallucinations was 3.5 times and 5.2 times greater in pramipexole dihydrochloride monohydrate tablets patients than placebo patients <65 years old, and >65 years old, respectively.
Post-marketing reports with medications used to treat Parkinson’s disease or RLS, including pramipexole dihydrochloride monohydrate tablets, indicate that patients may experience new or worsening mental status and behavioral changes, which may be severe, including psychotic-like behavior during treatment with pramipexole dihydrochloride monohydrate tablets or after starting or increasing the dose of pramipexole dihydrochloride monohydrate tablets. Other drugs prescribed to improve the symptoms of Parkinson’s disease or RLS can have similar effects on thinking and behaviour. This abnormal thinking and behaviour can consist of one or more of a variety of manifestations including paranoid ideation, delusions, hallucinations, confusion, psychotic-like behavior, symptoms of mania (e.g., insomnia, psychomotor agitation), disorientation, aggressive behavior, agitation, and delirium.
Patients with psychotic disorders should be treated with dopamine agonists only if the potential benefits outweigh the risks.
It is not recommended to combine a dopamine antagonist antipsychotic medication with pramipexole unless the potential benefit outweighs the risk. Alternatives as discussed should be considered (see 9.4 Drug-Drug Interactions).
In the RLS clinical program, one pramipexole-treated patient (of 889) reported hallucinations; this patient discontinued treatment and the symptoms resolved.
Suicidality
Patients and caregivers should be made aware of the inherent risk of suicidality in patients with Parkinson’s Disease and Restless Legs Syndrome. Such risk may not resolve when disease conditions see improvement.
Renal
Since pramipexole dihydrochloride monohydrate tablets is eliminated through the kidneys, caution should be exercised when prescribing APO-PRAMIPEXOLE to patients with renal insufficiency (see 4.2 Recommended Dose and Dosage Adjustment, Patients with renal impairment and 10.3 Pharmacokinetics, Renal Insufficiency).
Reproductive Health: Female and Male Potential Sexual Function/Reproduction
Fertility
No studies on the effect of pramipexole dihydrochloride monohydrate tablets on human fertility have been conducted.
In rat fertility studies, pramipexole at a dose of 2.5 mg/kg/day, prolonged the estrus cycle and inhibited implantation. Pramipexole, at a dose of 1.5 mg/kg/day (4.3 times the AUC observed in humans at the maximal recommended clinical dose of 1.5 mg t.i.d.) resulted in a high incidence of total resorption of embryos. These effects were associated with a reduction in serum levels of prolactin, a hormone necessary for implantation and maintenance of early pregnancy in rats, but not in rabbits and humans (see 16 NON-CLINICAL TOXICOLOGY).
Skin
Melanoma
Epidemiological studies have shown that patients with Parkinson’s disease have a higher risk (2- to approximately 6-fold higher) of developing melanoma than the general population. Whether the increased risk observed was due to Parkinson’s disease or other factors, such as drugs used to treat Parkinson’s disease, is unclear.
For the reasons stated above, patients and health-care providers are advised to monitor for melanomas frequently and on a regular basis when using APO-PRAMIPEXOLE for any indication. Ideally, periodic skin examination should be performed by appropriately qualified individuals (e.g., dermatologists).
7.1 Special Populations
7.1.1 Pregnant Women
There are no studies of pramipexole dihydrochloride monohydrate tablets in pregnant women. Because animal reproduction studies are not always predictive of human response, APO-PRAMIPEXOLE should be used during pregnancy only if the potential benefit outweighs the potential risk to the fetus.
7.1.2 Breast-feeding
It is unknown if pramipexole dihydrochloride monohydrate tablets is excreted in human milk. Precaution should be exercised because many drugs can be excreted in human milk. Since pramipexole dihydrochloride monohydrate tablets suppresses lactation, it should not be administered to mothers who wish to breast-feed infants.
A single-dose, radio-labelled study showed that drug-related materials were excreted into the breast milk of lactating rats. Concentrations of radioactivity in milk were three to six times higher than concentrations in plasma at equivalent time points.
7.1.3 Pediatrics
Pediatrics (≤ 18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Pramipexole dihydrochloride monohydrate tablets total oral clearance was approximately 25 to 30% lower in the elderly (aged 65 years and older) as a result of a decline in pramipexole renal clearance due to an age-related reduction in renal function. This resulted in an increase in elimination half-life from approximately 8.5 hours to 12 hours (see 4.2 Recommended Dose and Dosage Adjustment, Patients with Renal Impairment, 10.3 Pharmacokinetics).
In clinical studies, 40.8% (699 of 1715) of patients were between the ages of 65 and 75 years, and 6.5% (112 of 1715) of patients were >75 years old. There were no apparent differences in efficacy or safety between older and younger patients, except that the relative risk of hallucination associated with the use of pramipexole dihydrochloride monohydrate tablets was increased in the elderly.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Parkinson’s Disease
During the premarketing development of pramipexole dihydrochloride monohydrate tablets, patients enrolled in clinical trials had either early or advanced Parkinson’s disease. Apart from the severity and duration of their disease, the two populations differed in their use of concomitant levodopa therapy. Namely, patients with early disease did not receive concomitant levodopa therapy during treatment with pramipexole dihydrochloride monohydrate tablets, while those with advanced Parkinson’s disease did.
Because these two populations may have differential risk for various adverse events, adverse event data will be presented for both populations.
All controlled clinical trials performed during premarketing development (except one fixed dose study) used a titration design. Consequently, it was impossible to adequately evaluate the effects of a given dose on the incidence of adverse events.
The most commonly reported adverse reactions in patients with either early or advanced Parkinson’s disease more frequent with pramipexole dihydrochloride monohydrate tablets treatment than with placebo were nausea, dyskinesia, hypotension, dizziness, somnolence, insomnia, constipation, hallucination and confusion (see 3 SERIOUS WARNINGS AND PRECAUTION BOX, 7 WARNINGS AND PRECAUTIONS).
Restless Legs Syndrome
The most commonly reported adverse reactions with pramipexole dihydrochloride monohydrate tablets in patients with Restless Legs Syndrome were nausea and somnolence (see 3 SERIOUS WARNINGS AND PRECAUTION BOX).
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Parkinson’s Disease
Adverse Reactions Leading to Discontinuation of Treatment Early Parkinson’s disease
Approximately 12% of 388 patients treated with pramipexole dihydrochloride monohydrate tablets and 11% of 235 patients treated with placebo discontinued treatment due to adverse events. The events most commonly causing discontinuation of treatment were related to the nervous system, namely hallucinations (3.1% on pramipexole dihydrochloride monohydrate tablets vs 0.4% on placebo), dizziness (2.1% on pramipexole dihydrochloride monohydrate tablets vs 1.0% on placebo), somnolence (1.6% on pramipexole dihydrochloride monohydrate tablets vs 0% on placebo), headache and confusion (1.3% and 1.0%, respectively, on pramipexole dihydrochloride monohydrate tablets vs 0% on placebo), and to the gastrointestinal system (nausea 2.1% on pramipexole dihydrochloride monohydrate tablets vs 0.4% on placebo).
Advanced Parkinson’s disease
Approximately 12% of 260 patients treated with pramipexole dihydrochloride monohydrate tablets and 16% of 264 patients treated with placebo discontinued treatment due to adverse events. The events most commonly causing discontinuation of treatment were related to the nervous system, namely hallucinations (2.7% on pramipexole dihydrochloride monohydrate tablets vs 0.4% on placebo), dyskinesia (1.9% on pramipexole dihydrochloride monohydrate tablets vs 0.8% on placebo), dizziness (1.2% on pramipexole dihydrochloride monohydrate tablets vs 1.5% on placebo), confusion (1.2% on pramipexole dihydrochloride monohydrate tablets vs 2.3% on placebo, and to the cardiovascular system (postural [orthostatic] hypotension (2.3% on pramipexole dihydrochloride monohydrate tablets vs 1.1% on placebo)).
Most Frequent Adverse Events
Adverse events occurring with an incidence of greater than, or equal to, 10% and listed in decreasing order of frequency, were as follows:
Early Parkinson’s disease: nausea, dizziness, somnolence, insomnia, asthenia and constipation.
Advanced Parkinson’s disease: postural [orthostatic] hypotension, dyskinesia, insomnia, dizziness, hallucinations, accidental injury, dream abnormalities, constipation and confusion.
Incidence of Adverse Events in Placebo Controlled Trials
Table 4, lists treatment-emergent adverse events that were reported in the double-blind, placebo-controlled studies by ≥1% of patients treated with pramipexole dihydrochloride monohydrate tablets and were numerically more frequent than in the placebo group. Adverse events were usually mild or moderate in intensity.
TABLE 4 - ADVERSE EVENTS FROM PLACEBO-CONTROLLED STUDIES IN EARLY AND ADVANCED PARKINSON’S DISEASE (INCIDENCE OF EVENTS ≥1% IN PATIENTS TREATED WITH PRAMIPEXOLE DIHYDROCHLORIDE MONOHYDRATE TABLETS AND NUMERICALLY MORE FREQUENT THAN IN PATIENTS TREATED WITH PLACEBO)
| Therapy for Early Parkinson’s Disease | Therapy for Advanced Parkinson’s Disease | ||||||||||
| Body System/Adverse Event | Pramipexole dihydrochloride monohydrate tablets N = 388 % occurrence | Placebo N = 235 % occurrence | Pramipexole dihydrochloride monohydrate tablets† N = 260 % occurrence | Placebo† N = 264 % occurrence | |||||||
Body as a Whole Asthenia General edema Malaise Reaction unevaluable Fever Chest pain Accidental injury | 14 5 2 2 1 - - | 12 3 1 1 0 - - | 10 4 3 - - 3 17 | 8 3 2 - - 2 15 | |||||||
Cardiovascular System Postural hypotension | - | - | 53 | 48 | |||||||
Digestive System Nausea Constipation Anorexia Dysphagia Dry Mouth | 28 14 4 2 - | 18 6 2 0 - | - 10 - - 7 | - 9 - - 3 | |||||||
Metabolic & Nutritional System Peripheral edema Decreased weight Increased creatine PK | 5 2 - | 4 0 - | 2 - 1 | 1 - 0 | |||||||
Musculoskeletal System Arthritis Twitching Bursitis | - - - | - - - | 3 2 2 | 1 0 0 | |||||||
| Therapy for Early Parkinson’s Disease | Therapy for Advanced Parkinson’s Disease | ||||||||||
| Body System/Adverse Event | Pramipexole dihydrochloride monohydrate tablets N = 388 % occurrence | Placebo N = 235 % occurrence | Pramipexole dihydrochloride monohydrate tablets† N = 260 % occurrence | Placebo† N = 264 % occurrence | |||||||
| Myasthenia | - | - | 1 | 0 | |||||||
Nervous System Dizziness Somnolence Insomnia Hallucinations Confusion Amnesia Hyperesthesia Dystonia Thinking abnormalities Decreased libido Myoclonus Hypertonia Paranoid reaction Delusions Sleep disorders Dyskinesia Gait abnormalities Dream abnormalities | 25 22 17 9 4 4 3 2 2 1 1 - - - - - - - | 24 9 12 3 1 2 1 1 0 0 0 - - - - - - - | 26 9 27 17 10 6 - 8 3 - - 7 2 1 1 47 7 11 | 25 6 22 4 7 4 - 7 2 - - 6 0 0 0 31 5 10 | |||||||
Respiratory System Dyspnea Rhinitis Pneumonia | - - - | - - - | 4 3 2 | 3 1 0 | |||||||
Skin & Appendages Skin disorders | - | - | 2 | 1 | |||||||
Special Senses Vision Abnormalities Accommodation abnormalities Diplopia | 3 - - | 0 - - | 3 4 1 | 1 2 0 | |||||||
Urogenital System Impotence Urinary frequency Urinary tract infection | 2 - - | 1 - - | - 6 4 | - 3 3 | |||||||
| Therapy for Early Parkinson’s Disease | Therapy for Advanced Parkinson’s Disease | ||||||||
| Body System/Adverse Event | Pramipexole dihydrochloride monohydrate tablets N = 388 % occurrence | Placebo N = 235 % occurrence | Pramipexole dihydrochloride monohydrate tablets† N = 260 % occurrence | Placebo† N = 264 % occurrence | |||||
| Urinary incontinence | - | - | 2 | 1 | |||||
†Patients received concomitant levodopa
*Patients may have reported multiple adverse experiences during the study or at discontinuation, thus, patients may be included in more than one category.
Other Clinical Trial Adverse Drug Reactions (≥ 1%)
Other events reported by 1% or more of patients treated with pramipexole dihydrochloride monohydrate tablets but reported equally or more frequently in the placebo group were as follows:
Early Parkinson’s disease
Infection, accidental injury, headache, pain, tremor, back pain, syncope, postural hypotension, hypertonia, diarrhea, rash, ataxia, dry mouth, leg cramps, twitching, pharyngitis, sinusitis, sweating, rhinitis, urinary tract infection, vasodilation, flu syndrome, increased saliva, tooth disease, dyspnea, increased cough, gait abnormalities, urinary frequency, vomiting, allergic reaction, hypertension, pruritis, hypokinesia, increased creatine PK, nervousness, dream abnormalities, chest pain, neck pain, paresthesia, tachycardia, vertigo, voice alteration, conjunctivitis, paralysis, accommodation abnormalities, tinnitus, diplopia, and taste perversions.
Advanced Parkinson’s Disease
Nausea, pain, infection, headache, depression, tremor, hypokinesia, anorexia, back pain, dyspepsia, flatulence, ataxia, flu syndrome, sinusitis, diarrhea, myalgia, abdominal pain, anxiety, rash, paresthesia, hypertension, increased saliva, tooth disorder, apathy, hypotension, sweating, vasodilation, vomiting, increased cough, nervousness, pruritus, hyperesthesia, neck pain, syncope, arthralgia, dysphagia, palpitations, pharyngitis, vertigo, leg cramps, conjunctivitis, and lacrimation.
Adverse Events: Relationship to Age, Gender, and Race
Among the treatment-emergent adverse events in Parkinson’s disease patients treated with pramipexole dihydrochloride monohydrate tablets, hallucinations appeared to exhibit a positive relationship to age. No gender-related differences were observed. Only a small percentage (4%)
of patients enrolled were non-Caucasian, therefore, an evaluation of adverse events related to race is not possible.
Restless Legs Syndrome
Pramipexole dihydrochloride monohydrate tablets for treatment of RLS have been evaluated for safety in 889 patients, including 427 treated for over six months and 75 for over one year. The overall safety assessment focuses on the results of three double-blind, placebo-controlled trials, in which 575 patients with RLS were treated with pramipexole dihydrochloride monohydrate tablets for 3 to 12 weeks. The most commonly observed adverse events with pramipexole dihydrochloride monohydrate tablets in the treatment of RLS (observed in > 5% of pramipexole treated patients and at a rate at least twice that observed in placebo-treated patients) were nausea and somnolence. Occurrences of nausea and somnolence in clinical trials were generally mild and transient.
Approximately 7% of 575 patients treated with pramipexole dihydrochloride monohydrate tablets during the double-blind periods of three placebo-controlled trials discontinued treatment due to adverse events compared to 5% of 223 patients who received placebo. The adverse event most commonly causing discontinuation of treatment was nausea (1%).
Table 5: Treatment-Emergent Adverse-Event* Incidence in Double-Blind, Placebo-Controlled Trials in Restless Legs Syndrome (Events ≥ 2% of patients treated with Pramipexole dihydrochloride monohydrate tablets and numerically more frequent than in the placebo group):
Body System/ Adverse Event | Pramipexole dihydrochloride monohydrate tablets 0.125 – 0.75 mg/day (N=575) % | Placebo (N=223) % | ||
|---|---|---|---|---|
| Gastrointestinal disorders | ||||
| Nausea | 16 | 5 | ||
| Constipation | 4 | 1 | ||
| Diarrhea | 3 | 1 | ||
| Dry mouth | 3 | 1 | ||
| General disorders and administration site conditions | ||||
| Fatigue | 9 | 7 | ||
| Infections and infestations | ||||
| Influenza | 3 | 1 | ||
| Nervous system disorders | ||||
| Headache | 16 | 15 | ||
| Somnolence | 6 | 3 | ||
*Patients may have reported multiple adverse experiences during the study or at discontinuation; thus, patients may be included in more than one category.
In general, the frequency of nausea and fatigue was reduced with continued pramipexole dihydrochloride monohydrate tablets therapy. Other events reported by 2% or more of RLS patients treated with pramipexole dihydrochloride monohydrate tablets but equally or more frequently in the placebo group, were: vomiting, nasopharyngitis, back pain, pain in extremity, dizziness, and insomnia.
Table 6 summarizes data for adverse events that appeared to be dose related in the 12-week fixed dose study.
Table 6: Dose Related Adverse Events in a 12-Week Double-Blind, Placebo-Controlled Fixed Dose Study in Restless Legs Syndrome (occurring in ≥5% of all patients in the treatment phase)
Body System/ Adverse Event | Pramipexole dihydrochloride monohydrate tablets 0.25 mg (N=88) % | Pramipexole dihydrochloride monohydrate tablets 0.5 mg (N=80) % | Pramipexole dihydrochloride monohydrate tablets 0.75 mg (N=90) % | Placebo (n= 86) % | |||||
|---|---|---|---|---|---|---|---|---|---|
| Gastrointestinal disorders | |||||||||
| Nausea | 11.4 | 18.8 | 26.7 | 4.7 | |||||
| Diarrhea | 3.4 | 1.3 | 6.7 | 0 | |||||
| Dyspepsia | 3.4 | 1.3 | 4.4 | 7 | |||||
| Infections and infestations | |||||||||
| Influenza | 1.1 | 3.8 | 6.7 | 1.2 | |||||
| General disorders and administration site conditions | |||||||||
| Fatigue | 3.4 | 5.0 | 6.7 | 4.7 | |||||
| Psychiatric disorders | |||||||||
| Insomnia | 9.1 | 8.8 | 13.3 | 9.3 | |||||
| Abnormal dreams | 2.3 | 1.3 | 7.8 | 2.3 | |||||
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Nasal congestion | 0.0 | 2.5 | 5.6 | 1.2 | |||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Pain in extremity | 3.4 | 2.5 | 6.7 | 1.2 | |||||
Adverse Events: Relationship to Age, Gender, and Race
In RLS patients, nausea and fatigue, both generally transient, were more frequently reported by female than male. Less than 4% of patients enrolled were non-Caucasian, therefore, an evaluation of adverse events related to race in not possible.
8.3 Less Common Clinical Trial Adverse Reactions
Parkinson’s Disease
Other Adverse Events
During all Phase 2 and 3 Clinical Trials, pramipexole dihydrochloride monohydrate tablets has been administered to 1,715 subjects during the premarketing development program, 782 of who participated in double-blind, controlled studies. During these trials, all adverse events were recorded by the clinical investigators using terminology of their own choosing. To provide a meaningful estimate of the proportion of individuals having adverse events, similar types of events were grouped into a smaller number of standardized categories using modified COSTART dictionary terminology. These categories are used in the listing below.
The events listed below, within body-system categories in order of decreasing frequency, occurred in less than 1% of the subjects exposed to pramipexole dihydrochloride monohydrate tablets.
Body as a whole: fever, enlarged abdomen, rigid neck, no drug effect.
Cardiovascular system: palpitations, angina pectoris, atrial arrhythmia, peripheral vascular disease.
Digestive system: tongue discoloration, GI hemorrhage, fecal incontinence.
Endocrine system: diabetes mellitus.
Hemic & lymphatic system: ecchymosis.
Metabolic & nutritional system: gout, blood triglyceride increased.
Musculoskeletal system: bursitis, myasthenia.
Nervous system: apathy, libido decrease, paranoid reaction, akinesia, coordination abnormalities, speech disorder, hyperkinesia, neuralgia, delirium, mania, aggression.
Respiratory system: voice alteration, asthma, hemoptysis.
Skin & appendages: skin disorder, herpes simplex.
Special senses: tinnitus, taste perversion, otitis media, dry eye, ear disorder, hemianopia.
Urogenital system: urinary incontinence, dysuria, prostate disorder, kidney calculus.
In individual patients, hypotension may occur at the beginning of treatment, especially if pramipexole dihydrochloride monohydrate tablets is titrated too rapidly.
Restless Legs Syndrome
Other Adverse Events
During Phase 2 and 3 Clinical Trials, pramipexole dihydrochloride monohydrate tablets have been administered to 889 individuals in RLS clinical trials. During these trials, all adverse events were recorded by the clinical investigators using terminology of their own choosing; similar types of events were grouped into a smaller number of standardized categories using MedDRA dictionary terminology. These categories are used in the listing below. The events listed below occurred on at least two occasions (on one occasion if the event was serious) within the 889 individuals exposed to pramipexole dihydrochloride monohydrate tablets. All reported events, except those already listed above, are included, without regard to determination of a causal relationship to pramipexole dihydrochloride monohydrate tablets.
Blood and lymphatic system disorders: anemia.
Cardiac disorders: arrhythmia, coronary artery disease, myocardial infarction, myocardial ischemia, palpitations, tachycardia.
Congenital, familial, and genetic disorders: congenital atrial septal defect.
Ear and labyrinth disorders: tinnitus, vertigo.
Endocrine disorders: goiter, hypothyroidism.
Eye disorders: conjunctivitis, dry eye, eye irritation, eyelid edema, vision blurred, visual acuity reduced, visual disturbance.
Gastrointestinal disorders: abdominal discomfort, abdominal distension, abdominal pain, dyspepsia, enteritis, flatulence, gastroesophageal reflux disease, gastritis, hemorrhoids, inguinal hernia, irritable bowel syndrome, loose stools, toothache, umbilical hernia.
General disorders and administration site conditions: alcohol interaction, asthenia, chest pain, peripheral edema, feeling cold, feeling hot, inflammation localized, influenza-like illness, malaise, pain, pitting edema, pyrexia, thirst.
Hepatobiliary disorders: biliary colic, cholecystitis, cholelithiasis.
Immune system disorders: hypersensitivity, seasonal allergy.
Infections and infestations: Borrelia infection, bronchitis, cystitis, ear infection, fungal infection, gastroenteritis, herpes simplex, herpes zoster, hordeolum, laryngitis, localized infection, onychomycosis, otitis (externa and media), paronychia, pharyngitis, pneumonia, rhinitis, sinusitis, tonsillitis, tooth infection, urinary tract infection, vaginitis, viral infection.
Injury, poisoning and procedural complication: contusion, epicondylitis, failure of implant, fall, foot fracture, fractured sacrum, hip fracture, joint injury, joint sprain, limb injury, muscle strain, open fracture, radius fracture, sunburn, tendon rupture, thermal burn, wound, wrist fracture.
Investigations: alanine aminotransferase increased, aspartate aminotransferase increased, blood glucose increased, blood pressure increased, blood triglycerides increased, gammaglutamyltransferase increased, heart rate increased, heart rate irregular, weight decreased, weight increased.
Metabolism and nutrition disorders: anorexia, decreased appetite, hypercholesterolemia, hyperlipidemia, hypocalcemia, increased appetite.
Musculoskeletal and connective tissue disorders: arthralgia, bursitis, cervical spinal stenosis, intervertebral disc protrusion, intervertebral discitis, joint stiffness, localized osteoarthritis, lumbar spinal stenosis, muscle cramps, musculoskeletal stiffness, neck pain, myalgia, osteoporosis, sensation of heaviness, spinal osteoarthritis, tendonitis, toe deformity.
Neoplasms benign, malignant and unspecified: lung cancer metastatic, metastases to lung, ovarian cancer, prostatic adenoma, renal neoplasm, squamous cell carcinoma.
Nervous system disorders: balance disorder, carpal tunnel syndrome, cerebral ischemia, cervicobrachial syndrome, disturbance in attention, dizziness postural, dysgeusia, hypoesthesia, memory impairment, migraine, nerve compression, paraesthesia, Restless Legs Syndrome, sciatica, sedation, sinus headache, sudden onset of sleep, syncope, tension headache, transient ischemic attack, tremor.
Psychiatric disorders: abnormal dreams, agitation, anxiety, confusional state, depression, irritability, libido decreased, mood altered, nervousness, nightmare, restlessness, sleep disorder, stress symptoms.
Renal and urinary disorders: nocturia, pollakiuria, polyuria, renal colic.
Reproductive system and breast disorders: dysmenorrhea, menopausal symptoms, sexual dysfunction.
Respiratory, thoracic and mediastinal disorders: asthma, chronic obstructive airways disease (including exacerbation), cough, dyspnea, exertional dyspnea, epistaxis, nasal congestion, nasal septum deviation, pharyngolaryngeal pain, respiratory tract infection, sinus congestion, snoring.
Skin and subcutaneous tissue disorders: acne, eczema, erythema, hyperhidrosis, night sweats, photosensitivity allergic reaction, pruritus, rash, rosacea, seborrheic dermatitis.
Surgical and medical procedures: hysterectomy.
Vascular disorders: flushing, hematoma, hypertension, hypotension, orthostatic hypotension.
8.5 Post-Market Adverse Reactions
In addition to the adverse events reported during clinical trials, the following adverse reactions have been identified (essentially in Parkinson’s disease patients) during post-approval use of pramipexole dihydrochloride monohydrate tablets. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Sudden Onset of Sleep
Patients treated with pramipexole dihydrochloride monohydrate tablets have rarely reported suddenly falling asleep while engaged in activities of daily living; including operation of motor vehicles which has sometimes resulted in accidents (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
Impulse Control Disorders and Compulsive Behaviors
Abnormal behaviour (reflecting symptoms of impulse control disorders and compulsive behaviours), such as pathological (compulsive) gambling, hypersexuality, compulsive spending or buying, compulsive or binge eating, libido disorders, paranoia, and restlessness have been reported. These behavioural changes were generally reversible upon dose reduction or treatment discontinuation (see 7 WARNINGS AND PRECAUTIONS, Impulse Control Disorders and Compulsive Behaviors).
Dopamine Dysregulation Syndrome
Dopamine Dysregulation Syndrome (DDS) is an addictive disorder that has been observed in some patients treated with pramipexole dihydrochloride monohydrate tablets. Affected patients show compulsive abuse of dopaminergic drugs when using higher doses than are necessary for adequate control of motor symptoms of Parkinson’s disease. In some cases, this can lead to severe dyskinesia (see 7 WARNINGS AND PRECAUTIONS, Dopamine Dysregulation Syndrome).
Dopamine Agonist Withdrawal Syndrome
A cluster of symptoms, such as anxiety, fatigue, sweating, insomnia, panic attacks, depression, agitation, apathy, irritability, pain and drug craving, have been reported during dose reduction/ tapered discontinuation (see 7 WARNINGS AND PRECAUTIONS, Dopamine Agonist Withdrawal Syndrome (DAWS)).
Other Post-Marketing Reports
As a result of pooled clinical trial data analysis and review of post-marketing experience, hiccups, visual impairment (including diplopia), antecollis, libido disorders (pramipexole may uncommonly be associated with libido disorders (increased or decreased)), Restless Legs Augmentation Syndrome (see 7 WARNINGS AND PRECAUTIONS) and spontaneous penile erection have been reported.
Based on post-marketing experience, inappropriate antidiuretic hormone secretion has been reported. One of the diagnostic criteria of inappropriate antidiuretic hormone secretion is hyponatremia. Signs and symptoms of hyponatremia include headache, nausea, malaise, lethargy, difficulty concentrating, memory impairment, confusion, weakness, and unsteadiness, which may lead to falls. More severe and/or acute cases have been associated with hallucination, syncope, seizure, coma, respiratory arrest, and death.
In clinical studies and post-marketing experience, cardiac failure has been reported in patients with pramipexole. In a pharmacoepidemiological study, pramipexole use was associated with an increased risk of cardiac failure compared with non-use of pramipexole. A causal relationship between pramipexole and cardiac failure has not been demonstrated.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Pramipexole is bound to plasma proteins to a very low (< 20%) extent and little biotransformation is seen in humans. Therefore, interactions with other medication affecting plasma protein binding or elimination by biotransformation are unlikely.
The elimination of pramipexole is dependent on renal function. Medication that inhibits the active renal tubular secretion of basic (cationic) drugs or are themselves eliminated by active renal tubular secretion may interact with pramipexole dihydrochloride monohydrate tablets resulting in reduced clearance of either or both medications. In case of concomitant treatment with these kinds of drugs (incl. amantadine) a dose reduction may be necessary (see 4.2 Recommended Dose and Dosage Adjustment, Patients with Renal Impairment, 9.4 Drug-Drug Interactions, Table 7 and 10.3 Pharmacokinetics).
Pramipexole co-administered with inhibitors of cytochrome P450 enzymes are not expected to affect pramipexole elimination because pramipexole is not appreciably metabolized by these enzymes in vivo or in vitro (see 9.4 Drug-Drug Interactions, Table 7).
As anticholinergics are mainly eliminated by hepatic metabolism, pharmacokinetic drug-drug interactions with pramipexole are rather unlikely.
Caution needs to be advised when patients are taking other sedating medication or alcohol in combination with APO-PRAMIPEXOLE (see sections 9.3 Drug-Behavioral Interactions and 9.4 Drug-Drug Interactions). In addition, co-administration of dopamine-antagonistic antipsychotic medicinal products with pramipexole is not recommended (see 7 WARNINGS AND PRECAUTIONS, Hallucinations and Psychotic-like behavior).
When APO-PRAMIPEXOLE is co-administered with some other drugs, dose adjustments may be considered, e.g., for antiparkinsonian drugs.
For more details, please see section 9.4 Drug-Drug Interactions.
9.3 Drug-Behavioural Interactions
Because of possible additive effects, caution should be advised when patients are taking other sedating medication or alcohol in combination with APO-PRAMIPEXOLE and when taking concomitant medication that increase plasma levels of pramipexole (e.g., cimetidine) (see 9.4 Drug-Drug Interactions).
9.4 Drug-Drug Interactions
The drugs listed in table 7 are based on information collected in clinical studies, interaction case reports, or pharmacological properties of the drug that may be used. See Table 7 below and 10.3 Pharmacokinetics for more information.
Table 7 - Established or Potential Pharmacokinetic Interactions
| Pramipexole dihydrochloride monohydrate | Source of Evidence | Effect | Clinical comment |
| Antiparkinsonian drugs | |||
| Levodopa/carbidopa | CT | Pramipexole increases levodopa Cmax by about 40% and reduces Tmax from 2.5 to 0.5 hours. No change in total exposure (AUC) was observed. Levodopa/carbidopa has no effect on the pharmacokinetics of pramipexole in healthy volunteers. | The combined use of pramipexole and levodopa increases the frequency of hallucination. Dosage adjustment, even discontinuation, may be necessary. While increasing the dose of pramipexole dihydrochloride monohydrate tablets in Parkinson’s disease patients it is recommended that the dosage of levodopa is reduced and the dosage of other anti-parkinsonian medication is kept constant. |
| Selegiline | CT | Selegiline has no effect on the pharmacokinetics of pramipexole in volunteers. | |
| Pramipexole dihydrochloride monohydrate | Source of Evidence | Effect | Clinical comment |
| Amantadine | CT | Amantadine inhibits the renal cationic transport system. Amantadine might alter the clearance of pramipexole. | Dosage adjustment may be necessary. See below. |
| Anticholinergics | |||
| Anticholinergics | T | As anticholinergics are mainly eliminated by hepatic metabolism, pharmacokinetic drug-drug interactions with pramipexole are rather unlikely. | |
| Other drugs eliminated via renal secretion | |||
Drugs eliminate via the renal cationic transport system Amantadine Cimetidine Ranitidine Diltiazem Triamterene Verapamil Quinidine Quinine | CT | These drugs inhibit the renal tubular secretion of organic bases via the cationic transport system. They reduce the renal clearance of pramipexole to various degrees. | Dosage adjustment should be considered if concomitant treatment is necessary. Dosage reduction is necessary if adverse reactions, such as dyskinesia, agitation, or hallucination, are observed. |
Drugs eliminate via the renal anionic transport system Probenecid Cephalosporins Penicillins Indomethacin Hydrochlorothiazide Chloropramide | T | These drugs inhibit the renal tubular secretion of organic bases via the anionic transport system. They are unlikely to reduce the renal clearance of pramipexole. | Dosage adjustment is not necessary. |
| Interactions mediated by CYP isoenzymes | |||
| Pramipexole dihydrochloride monohydrate | Source of Evidence | Effect | Clinical comment |
| Drugs metabolized by CYP isoenzymes | T | Inhibitors of CYP isoenzymes are not expected to affect the elimination of pramipexole. Pramipexole has no inhibitory action on CYP1A2, CYP2C9, CYP2C19, CYP2E1, and CYP3A4. Inhibition of CYP2D6 is observed with an apparent Ki of 30 mcM, suggesting that pramipexole dihydrochloride monohydrate tablets will not inhibit CYP enzymes at plasma concentrations following the highest recommended clinical dose (1.5 mg tid). | |
| Dopamine antagonists | |||
Neuroleptics, e.g., phenothiazines, butyrophenones, thioxanthines Metoclopramide | T | Pramipexole is a dopamine agonist. Dopamine antagonists reduce its therapeutic effects. | Co-administration of dopamine-antagonistic antipsychotic medicinal products with pramipexole is not recommended, 7 WARNINGS AND PRECAUTIONS) Pramipexole can exacerbate psychotic symptoms. |
| Miscellaneous | |||
| Sedating medication or alcohol | T | Possible additive effects. | Because of possible additive effects, caution should be advised when patients are taking other sedating medication or alcohol in combination with APO-PRAMIPEXOLE. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
APO-PRAMIPEXOLE (pramipexole dihydrochloride monohydrate tablets) is a non ergot dopamine agonist with high in vitro specificity at the D2 subfamily of dopamine receptors. Pramipexole is a full agonist and exhibits higher affinity to the D3 receptor subtypes (which are in prominent distribution within the mesolimbic area) than to D2 or D4 receptor subtypes. While pramipexole dihydrochloride monohydrate tablets exhibits high affinity for the dopamine D2 receptor subfamily, it has low affinity for α2 adrenergic receptors and negligible or undetectable affinity for other dopaminergic, adrenergic, histaminergic, adenosine and benzodiazepine receptors.
The ability of pramipexole to alleviate the signs and symptoms of Parkinson’s disease is believed to be related to its ability to stimulate dopamine receptors in the striatum. This assumption is supported by a dose-dependent antagonism of Parkinsonian symptoms in rhesus monkeys pre-treated with the neurotoxin N-methyl-4-phenyl-1,2,3,6-tetrahydropyridine (MPTP) which destroys dopamine cell bodies in the substantia nigra.
The precise mechanism of action of pramipexole dihydrochloride monohydrate tablets as a treatment for Restless Legs Syndrome is not known. Although the pathophysiology of Restless Legs Syndrome is largely unknown, neuropharmacological evidence suggests primary dopaminergic system involvement. Positron emission tomographic (PET) studies suggest that a mild striatal presynaptic dopaminergic dysfunction may be involved in the pathogenesis of Restless Legs Syndrome.
In human volunteers a dose-dependent decrease in prolactin was observed.
10.2 Pharmacodynamics
Receptor binding studies
Preclinical studies, which compared the relative pharmacological activities and receptor binding affinities (displacement of [3H]spiroperidol) of the pramipexole racemate and its optical isomers, showed the levorotational (-) enantiomer to be more potent.
Studies with cloned human receptors, expressed in cultured Chinese hamster ovary (CHO) cells, indicate that, within the recently discovered D2 receptor subfamily, pramipexole binds with highest affinity to the D3 subtype (Ki=0.5 nM). Pramipexole has approximately a 5- to 10-fold preferential affinity for the D3 receptor when compared to its affinities for the high affinity forms of the D2S, D2L and D4 subtypes (Ki values: 3.3, 3.9 and 5.1 nM, respectively). As is true for other dopamine agonists, exposure of the receptor to a non-hydrolyzable analog of GTP decreases the affinity of pramipexole for the cloned D3 receptor much less than it does for the cloned D2 or D4 subtypes. The small GTP-shift for agonists of the D3 receptor site is an indication of the weak coupling of this receptor to the G-protein second messenger system in CHO cells.
Besides binding to the dopamine-D2 receptor subfamily, pramipexole has a low affinity for α2 adrenoreceptors and a very low affinity for histamine H2 and serotonin 5-HT1A receptors. Its affinity for other dopaminergic, adrenergic, histaminergic, serotonergic, cholinergic, glutamatergic, adenosine and benzodiazepine receptors is negligible or undetectable.
Receptor binding autoradiography with [3H] pramipexole (5 nM, 62 Ci/mmole) was used to evaluate the distribution of pramipexole binding sites within the rat brain. The highest concentrations of [3H] pramipexole binding sites were found in the Islets of Calleja, previously reported to contain D3, but not D2 or D4 mRNA. [3H]Pramipexole binding was also high in other mesolimbic areas, such as the nucleus accumbens, olfactory tubercle, and amygdala. [3H]Pramipexole binding was also high in caudate, although slightly less than in mesolimbic areas. Striatal areas have higher D2 : D3 mRNA ratios than do mesolimbic regions. Fewer [3H]pramipexole binding sites were found in VTA and substantia nigra, areas rich in cell bodies for dopamine neurons. Although it is likely that much of this [3H]pramipexole binding reflects D2 receptors, the relatively high mesolimbic binding could reflect the preferential affinity pramipexole has for the D3 receptor subtype.
Animal Studies
Antagonism of Reserpine-Induced Akinesia
Reserpine treatment leads to depletion of monoamines, including dopamine. Animals so treated are essentially akinetic, but can be activated by dopamine agonists.
Pramipexole, (30 mcmole/kg = 9 mg/kg IP) stimulated locomotor activity in reserpinized mice. These data are consistent with a pramipexole-induced stimulation of postsynaptic dopamine receptors in the basal ganglia.
Antagonism of Haloperidol-Induced Catalepsy
The dopamine receptor antagonist haloperidol induces hypomotility, rigidity, and catalepsy in the rat. The cataleptic behaviour is regard to be highly predictive of neuroleptic-induced Parkinson like extrapyramidal side effects.
In one study, rats were injected with haloperidol, 1 mg/kg. Rats were considered cataleptic if they maintained a position with their forepaws elevated on a 6 to 8 cm high rod for at least 30 seconds two hours after haloperidol. Pramipexole dose-dependently suppressed catalepsy, with an ED50 of 4.4 mg/kg SC.
In a second study, catalepsy, produced by 5 mcmole/kg SC (= 2 mg/kg) of haloperidol, was scored by measuring the time rats remained with their forepaws on a squared wooden cube. Pramipexole (50 mcmole/kg = 15.1 mg/kg) readily blocked the catalepsy.
Rotational Behavior in 6-Hydroxydopamine (6-OHDA) Lesioned Rats
When 6-OHDA is injected unilaterally into the medial forebrain bundle of rats, a selective degeneration of presynaptic dopaminergic neurons occurs; rendering the animals essentially hemi-Parkinsonian. The postsynaptic neurons at the site of the lesion become hypersensitive to dopamine agonists. When dopamine agonists are administered to lesioned rats, a contralateral rotational behaviour can be observed. The number of rotations is evaluated in a rotameter.
In an initial study, pramipexole and, for comparison, apomorphine was tested in doses of 0.01 to 0.1 mg/kg. The D1- and D2-selective dopamine antagonists, SCH 23390 and haloperidol, respectively, were used to determine the subfamily of receptors involved. All compounds were administered SC.
Both pramipexole (ED50 0.026 mg/kg, maximum effect 80 to 140 minutes after administration) and apomorphine (ED50 0.030 mg/kg, maximum effect 5 to 65 minutes after administration) induced contralateral turning behaviour in 6-OHDA-lesioned rats. Whereas the effect of apomorphine ceased after 80 minutes, pramipexole was effective throughout the recording period of 2 hours.
Pretreatment with 0.05 mg/kg of haloperidol markedly attenuated the effect of pramipexole (0.05 mg/kg). The very high dose of 2 mg/kg of SCH 23390 also inhibited the effect, albeit to a smaller extent.
A second study confirmed the potent and long-lasting effects of pramipexole in this animal model of Parkinson’s disease; maximal effects occurred with a dose of 0.3 mcmoles/kg (= 0.09 mg/kg) SC. Higher doses produced less effect.
MPTP-Induced Parkinsonian Symptoms in Rhesus Monkeys
MPTP (n-methyl-4-phenyl-1,2,3,6-tetrahydropyridine) is a highly selective neurotoxin which destroys the dopamine cell bodies in the zona compacta of the substantia nigra. The chronic dopamine depletion in the substantia nigra, results in a syndrome which resembles severe Parkinsonism, observed in patients. The effect of MPTP is irreversible. Due to chronic denervation, the postsynaptic dopamine D2 receptors become hypersensitive. A presynaptic action of a compound in the substantia nigra is excluded in this model because the presynaptic neurons have been destroyed.
Pramipexole (0.03 to 0.1 mg/kg IM) dose-dependently reversed the Parkinson-like symptoms in MPTP-treated rhesus monkeys. The dose which antagonized the symptoms in 50% of the animals (ED50) was 0.045 mg/kg IM. A dose of 0.06 mg/kg was effective in all animals. The animals’ locomotor activity, recorded with an electronic device mounted on their arm, returned to normal and did not exceed that of monkeys not pretreated with MPTP. Stereotyped movements, abnormal excitation, salivation, or sedation were not observed in the dose range tested. A dose of 0.1 mg/kg IM was effective for more than 5h.
In another study, oral doses of 0.05 to 0.1 mg/kg of pramipexole were evaluated in MPTP treated rhesus monkeys. At a dose of 0.075 mg/kg, the compound completely reversed the Parkinsonian symptoms. The duration of action varied between 5 and 24 hours.
10.3 Pharmacokinetics
Absorption:
Following oral administration, pramipexole is rapidly absorbed reaching peak concentrations between 1 and 3 hours. The absolute bioavailability of pramipexole is greater than 90%. Pramipexole can be administered with or without food. A high-fat meal did not affect the extent of pramipexole absorption (AUC and Cmax) in healthy volunteers, although the time to maximal plasma concentration (Tmax) was increased by about 1 hour.
Pramipexole displays linear pharmacokinetics over the range of doses that are recommended for patients with Parkinson’s disease.
Distribution:
Pramipexole is extensively distributed, having a volume of distribution of about 500 L. Protein binding is less than 20% in plasma; with albumin accounting for most of the protein binding in human serum. Pramipexole distributes into red blood cells as indicated by an erythrocyte to plasma ratio of approximately 2.0 and a blood to plasma ratio of approximately 1.5. Consistent with the large volume of distribution in humans, whole body autoradiography and brain tissue levels in rats indicated that pramipexole was widely distributed throughout the body, including the brain.
Metabolism and Elimination:
Urinary excretion is the major route of pramipexole elimination. Approximately 88% of a 14C-labelled dose was recovered in the urine and less than 2% in the feces following single intravenous and oral doses in healthy volunteers. The terminal elimination half-life was about 8.5 hours in young volunteers (mean age 30 years) and about 12 hours in elderly volunteers (mean age 70 years). Approximately 90% of the recovered 14C-labelled dose was unchanged drug; with no specific metabolites having been identified in the remaining 10% of the recovered radio-labelled dose. Pramipexole is the levorotational (-) enantiomer, and no measurable chiral inversion or racemization occurs in vivo.
The renal clearance of pramipexole is approximately 400 mL/min, approximately three times higher than the glomerular filtration rate. Thus, pramipexole is secreted by the renal tubules, probably by the organic cation transport system.
Special Populations and Conditions
Because therapy with pramipexole is initiated at a subtherapeutic dose and gradually titrated according to clinical tolerability to obtain optimal therapeutic effect, adjustment of the initial dose based on gender, weight, or age is not necessary. However, renal insufficiency, which can cause a large decrease in the ability to eliminate pramipexole, may necessitate dosage adjustment.
- Early vs. advanced Parkinson’s disease patients: The pharmacokinetics of pramipexole was comparable between early and advanced Parkinson’s disease patients.
- Healthy Volunteers: In a clinical trial with healthy volunteers, where pramipexole extended release tablets were titrated faster than recommended (every 3 days) up to 4.5 mg per day, an increase in blood pressure and heart rate was observed. Such effect was not observed in patient studies.
- Restless Legs Syndrome Patients: A cross-study comparison of data suggests that the pharmacokinetic profile of pramipexole administered once daily in RLS patients is generally consistent with the pharmacokinetic profile of pramipexole in healthy volunteers.
- Pediatrics: The pharmacokinetics of pramipexole in the pediatric population has not been evaluated.
Geriatrics: Renal function declines with age. Since pramipexole clearance is correlated with renal function, the drug’s total oral clearance was approximately 25% to 30% lower in elderly (aged 65 years or older) compared with young healthy volunteers (aged less than 40 years). The decline in clearance resulted in an increase in elimination half-life from approximately 8.5 hours in young volunteers (mean age 30 years) to 12 hours in
- Sex: Pramipexole renal clearance is about 30% lower in women than in men, most of this difference can be accounted for by differences in body weight. The reduced clearance resulted in a 16 to 42% increase in AUC and a 2 to 10% increase in Cmax. The differences remained constant over the age range of 20 to 80 years. The difference in pramipexole half-life between males and females was less than 10%.
- Ethnic Origin: A retrospective population pharmacokinetic analysis on data from patients with Parkinson’s disease receiving immediate-release pramipexole suggests that oral clearance of pramipexole is 17% higher in black male patients compared to white male patients.
- Hepatic Insufficiency: The potential influence of hepatic insufficiency on pramipexole pharmacokinetics has not been evaluated; however, it is considered to be small. Since approximately 90% of the recovered 14C-labelled dose was excreted in the urine as unchanged drug, hepatic impairment would not be expected to have a significant effect on pramipexole elimination.
- Renal Insufficiency: The clearance of pramipexole was about 75% lower in patients with severe renal impairment (creatinine clearance approximately 20 mL/min) and about 60% lower in patients with moderate impairment (creatinine clearance approximately 40 mL/min) compared with healthy volunteers. A lower starting and maintenance dose is recommended in patients with renal impairment (see 4.2 Recommended Dose and Dosage Adjustment, Dosing in Patients with Renal Impairment). In patients with varying degrees of renal impairment, pramipexole clearance correlates well with creatinine clearance. Therefore, creatinine clearance can be used as a predictor of the extent of decrease in pramipexole clearance. As pramipexole clearance is reduced even more in dialysis patients (N=7), than in patients with severe renal impairment, the administration of pramipexole to patients with end stage renal disease is not recommended.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature, 15°C to 30°C.
As with all medications, APO-PRAMIPEXOLE should be kept safely out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance:
Proper name: Pramipexole dihydrochloride monohydrate
Chemical name: (S)-2-Amino-4, 5,6,7-tetrahydro-6-propylamino-benzothiazole dihydrochloride monohydrate
Molecular formula and molecular mass: C10H17N3S.2HCl.H2O and (302.26 g/mol)
Structural formula:
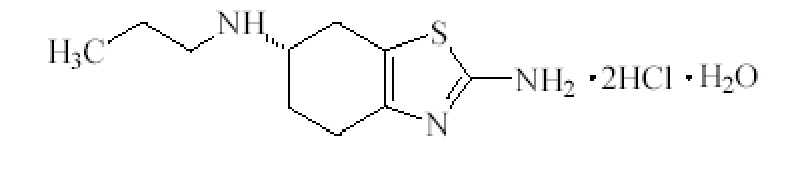
Physicochemical properties:
| Description: | White to off-white powder. |
| pH: | 3.99 (1% solution in water) |
| pKa: | pKa1 = 9.5 ± 0.2 pKa2 = 5.6 ± 0.4 |
| Specific Optical Rotation: | [α]D20 = -67.2 o (c = 1 in methanol) |
| UV absorption maxima and molar absorptivity: | λmax= 264 nm; γ = 7.9 x10³ (in methanol) |
| Water/Octanol Partition Coefficient: | Log P (Octanol/ water): 1.42±0.29 (calculated for free base) |
| Melting Point: | 296°C - 298°C |
Solubility in common solvents:
| Solvent | Solubility (Parts of Solvent Required for 1 Part of Solute) | Descriptive Term (as defined in the USP) |
| Water | From 10 to 30 | Soluble |
| Methanol | From 10 to 30 | Soluble |
Quantitative aqueous pH solubility profile at ambient temperature:
| Solvent | pH Value Final | Solubility mg/mL | Highest Dose (1.5 mg) /Solubility mL |
| H2O | 4.2 | > 20 | < 1 |
| 0.1N HCl | 1.2 | > 20 | < 1 |
| 0.01N HCl | 3.0 | > 20 | < 1 |
| SGF | 1.2 | > 20 | < 1 |
| pH2.5 Buffer | 2.8 | > 20 | < 1 |
| pH3.5 Buffer | 4.2 | > 20 | < 1 |
| pH4.5 Buffer | 4.3 | > 20 | < 1 |
| pH5.5 Buffer | 4.4 | > 20 | < 1 |
| pH6.0 Buffer | 4.5 | > 20 | < 1 |
| pH6.8 Buffer | 4.9 | > 20 | < 1 |
| pH7.2 Buffer | 5.2 | > 20 | < 1 |
| pH7.5 Buffer | 5.4 | > 20 | < 1 |
* all buffers are potassium phosphate buffer (0.05M)
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Parkinson’s Disease
Table 8 - Summary of patient demographics for clinical trials in Parkinson’s Disease
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 9158-95-025 | double-blind, placebo-controlled, parallel study | Pramipexole dihydrochloride monohydrate tablets, 0.375 mg titrated to a maximally tolerated dose, but no higher than 4.5 mg/day, oral tablets, 7 Week Dose escalation and 6 month maintenance | Pramipexole dihydrochloride monohydrate tablets (N = 164) placebo (N = 171). | 25 years of age or older | m&f |
| TR: 7217-95-037 | double-blind, placebo-controlled parallel trial | Pramipexole dihydrochloride monohydrate tablets (1.5 mg, 3.0 mg, | n=264 (randomized to 1 of 4 pramipexole dihydrochloride | 30 years of age or older | m&f |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 4.5 mg, or 6.0 mg per day) or placebo, a 6-week dose escalation period and a 4-week maintenance period. | monohydrate tablets doses or Placebo) | ||||
| 248.320 | primary assessments were the UPDRS and daily diaries that quantified amounts of “on” and “off” times | Pramipexole dihydrochloride monohydrate tablets, 0.375 mg titrated to a maximally tolerated dose, but no higher than 4.5 mg/day, oral tablets, 7 Week Dose escalation and 6 month maintenance | N = 181 on pramipexole dihydrochloride monohydrate tablets, N = 179 on placebo | Mean age 63.3 years | m&f |
Study demographics and trial design
Up to February 29, 1996, 1715 patients have been exposed to pramipexole dihydrochloride monohydrate tablets, with 669 patients being exposed for over one year and 222 patients being exposed for over two years.
The effectiveness of pramipexole dihydrochloride monohydrate tablets in the treatment of Parkinson’s disease was evaluated in a multinational drug development program consisting of seven randomized controlled trials. Three were conducted in patients with early Parkinson’s disease who were not receiving concomitant levodopa, and four were conducted in patients with advanced Parkinson’s disease who were receiving concomitant levodopa. Among these seven studies, three Phase 3 studies provide the most persuasive evidence of pramipexole dihydrochloride monohydrate tablets’ effectiveness in the management of patients with Parkinson’s disease who were or were not receiving concomitant levodopa. Two of the trials enrolled patients with early Parkinson’s disease (not receiving levodopa), and one enrolled patients with advanced Parkinson’s disease who were receiving maximally tolerated doses of levodopa.
Study results
In all studies, the Unified Parkinson’s Disease Rating Scale (UPDRS), or one or more of its subscales, served as the primary outcome assessment measure.
Studies in patients with early Parkinson’s disease
Patients in the two studies with early Parkinson’s disease had mean disease duration of 2 years, limited or no prior exposure to levodopa, and were not experiencing the “on-off’ phenomenon and dyskinesia characteristics of later stages of the disease.
Study Number 9158-95-025
One of the trials was a double-blind, placebo-controlled, parallel study in which patients were randomized to pramipexole dihydrochloride monohydrate tablets (N = 164) or placebo (N = 171). The trial consisted of a 7-week dose escalation period and a 6-month maintenance period. Patients could be on selegiline and/or anticholinergics but not on levodopa products. Patients treated with pramipexole dihydrochloride monohydrate tablets had a starting dose of 0.375 mg/day and were titrated to a maximally tolerated dose, but no higher than 4.5 mg/day, administered in three divided doses. At the end of the 6-month maintenance period, the mean improvement from baseline on the UPDRS Part II (activities of daily living [ADL] subscale) score was 1.9 in the pramipexole dihydrochloride monohydrate tablets group and -0.4 in the placebo group. The mean improvement from baseline on the UPDRS part III (motor subscale) was 5.0 in the pramipexole dihydrochloride monohydrate tablets group and -0.8 in the placebo group. Both differences were statistically significant. The mean daily dose of pramipexole dihydrochloride monohydrate tablets during the maintenance period was 3.8 mg/day.
The difference in mean daily dose between males and females was less than 10%. Patients >75 years (N = 26) received the same mean daily dose as younger patients.
Study Number: TR: 7217-95-037
The second early Parkinson’s disease study was a double-blind, placebo-controlled parallel trial which Study Number evaluated dose-response relationships. It consisted of a 6-week dose escalation period and a 4-week maintenance period. A total of 264 patients were enrolled. Patients could be on selegiline, anticholinergics, amantadine, or any combination of these, but not on levodopa products. Patients were randomized to 1 of 4 fixed doses of pramipexole dihydrochloride monohydrate tablets (1.5 mg, 3.0 mg, 4.5 mg, or 6.0 mg per day) or placebo. No dose-response relationship was demonstrated. The between treatment differences on both parts of the UPDRS were statistically significant in favour of pramipexole dihydrochloride monohydrate tablets at all doses.
In both studies in early Parkinson’s disease patients, no differences in effectiveness were detected based upon age or gender. Patients receiving selegiline or anticholinergics had responses similar to patients not receiving these drugs.
To date, results comparing pramipexole dihydrochloride monohydrate tablets to levodopa are not available.
Studies in patients with advanced Parkinson’s disease
Study Number: 248.320
In the advanced Parkinson’s disease study, the primary assessments were the UPDRS and daily diaries that quantified amounts of “on” and “off” times.
Patients (N = 181 on pramipexole dihydrochloride monohydrate tablets, N = 179 on placebo) had a mean disease duration of 9 years, had been exposed to levodopa for a mean of 8 years, received concomitant levodopa during the trial and had “on-off” periods. Patients could additionally be on selegiline, anticholinergics, amantadine, or any combination of these. The study consisted of a 7-week dose-escalation period and a 6-month maintenance period. Patients treated with pramipexole dihydrochloride monohydrate tablets had a starting dose of 0.375 mg/day and were titrated to a maximally tolerated dose but no higher than 4.5 mg/day, administered in three divided doses. At the end of the 6-months maintenance period, the mean improvement from baseline on the UPDRS part II (ADL) score was 2.7 in the pramipexole dihydrochloride monohydrate tablets group and 0.5 in the placebo group. The mean improvement from baseline on the UPDRS part III (motor) score was 5.6 in the pramipexole dihydrochloride monohydrate tablets group and 2.8 in the placebo group. Both differences were statistically significant. The mean daily dose of pramipexole dihydrochloride monohydrate tablets during the maintenance period was 3.5 mg/day. The dose of levodopa could be reduced if dyskinesia or hallucinations developed. Levodopa dose reduction occurred in 76% and 54% of pramipexole dihydrochloride monohydrate tablets and placebo-treated patients, respectively. On average, the percent decrease was 27% in the pramipexole dihydrochloride monohydrate tablets group and 5% in the placebo group.
In females the mean daily dose was approximately 10% lower than in male patients. Patients aged over 75 years (N = 24) had approximately a 10% lower dose than younger patients.
The mean number of “off” hours per day during baseline was approximately 6 hours for both groups. Throughout the trial, patients treated with pramipexole dihydrochloride monohydrate tablets had a mean “off” period of approximately 4 hours, while the duration of “off” periods remained essentially unchanged in the placebo-treated subjects.
No differences in effectiveness were detected based upon age or gender.
Restless Legs Syndrome
Table 9 - Summary of patient demographics for clinical trials in Restless Legs Syndrome
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
| 248.543 | Fixed dose, randomized, double-blind, placebo- controlled trials | Pramipexole dihydrochloride monohydrate tablets (n=254) had a starting dose of 0.125 mg/day and were titrated to one of the three randomized doses (0.25, 0.50, 0.75 mg/day) in the first three weeks of the study, 12 weeks duration | Enrolled 345 Pramipexole dihydrochloride monohydrate tablets N = 254 analysed placebo (N = 85 analysed | 55 years (range of 18 to 81 years) | m&f |
| 248.546 | randomized-withdrawal study, double-blind, placebo- controlled trials | Pramipexole dihydrochloride monohydrate tablets, Oral (0.125 mg, 0.25 mg, 0.5 mg or 0.75 mg), for 12 weeks | Pramipexole dihydrochloride monohydrate tablets (n=78) placebo (n=69) | 55 years (range of 18 to 81 years) | m&f |
| 248.520 | randomized, double-blind, placebo- controlled trials comparing a flexible dose of pramipexole dihydrochloride monohydrate tablets to placebo | Pramipexole dihydrochloride monohydrate tablets, Oral (0.125 mg, 0.25 mg, 0.5 mg or 0.75 mg), for 6 Weeks | N=345 Placebo 115 (Analysed 114) Pramipexole 230 (Analysed 214) Placebo | 55 years (range of 18 to 81 years) | m&f |
| 248.515 | randomized, double-blind, placebo- controlled trials, comparing 4 fixed doses of pramipexole dihydrochloride | Pramipexole dihydrochloride monohydrate tablets, Oral (0.125 mg, 0.25 mg, 0.5 mg or 0.75 mg), for 3 Weeks | Enrolled 141 Pramipexole n=87 Placebo n= 22 (Approximately 20 patients were randomized to | 55 years (range of 18 to 81 years) | m&f |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex | |
|---|---|---|---|---|---|---|
| monohydrate tablets, 0.125mg, 0.25 mg, 0.5 mg, and 0.75 mg, to placebo | each of the 5 dose groups) | |||||
The efficacy of pramipexole dihydrochloride monohydrate tablets in the treatment of Restless Legs Syndrome (RLS) was evaluated in a multinational drug development program consisting of 4 randomized, double-blind, placebo- controlled trials. This program included approximately 1000 patients with moderate to severe RLS; patients with RLS secondary to other conditions (e.g., pregnancy, renal failure, and anaemia) were excluded. All patients were administered pramipexole dihydrochloride monohydrate tablets (0.125 mg, 0.25 mg, 0.5 mg, or 0.75 mg) or placebo once daily 2 to 3 hours before going to bed. Across the 4 studies, the mean duration of RLS was 4.6 years (range of 0 to 56 years), mean age was approximately 55 years (range of 18 to 81 years), and approximately 66 % of patients were women.
The two outcome measures used to assess the effect of treatment were the International RLS Rating Scale (IRLS Scale) and a Clinical Global Impression - Improvement (CGI-I) assessment. The IRLS Scale contains 10 items designed to assess the severity of sensory and motor symptoms, sleep disturbance, daytime somnolence, and impact on activities of daily living and mood associated with RLS. The range of scores is 0 to 40, with 0 being absence of RLS symptoms and 40 the most severe symptoms. The CGI-I is designed to assess clinical progress (global improvement) on a 7-point scale.
In Study 248.543 fixed doses of pramipexole dihydrochloride monohydrate tablets were compared to placebo in a study of 12 weeks duration. A total of 344 patients were randomized equally to the 4 treatment groups. Patients treated with pramipexole dihydrochloride monohydrate tablets (n=254) had a starting dose of 0.125 mg/day and were titrated to one of the three randomized doses (0.25, 0.50, 0.75 mg/day) in the first three weeks of the study. The mean improvement from baseline on the IRLS Scale total score and the percentage of CGI-I responders for each of the pramipexole dihydrochloride monohydrate tablets treatment groups compared to placebo are summarized in Table 10.
All treatment groups reached statistically significant superiority compared to placebo for both endpoints. There was no clear evidence of a dose-response across the 3 randomized dose groups.
Table 10: Mean changes from baseline to Week 12 IRLS Score and CGI-I
| Pramipexole dihydrochloride monohydrate tablets 0.25 mg | Pramipexole dihydrochloride monohydrate tablets 0.5 mg | Pramipexole dihydrochloride monohydrate tablets 0.75 mg | Pramipexole dihydrochloride monohydrate tablets total | Placebo | |
|---|---|---|---|---|---|
| No. of patients | 88 | 79 | 87 | 254 | 85 |
| IRLS Score | -13.1 | -13.4 | -14.4 | -13.6 | -9.4 |
| CGI-I responders * | 74.7% | 68% | 72.9% | 72% | 51.2% |
*CGI-I responders = “much improved” and “very much improved”.
Study 248.546 was a randomized-withdrawal study, designed to demonstrate the sustained efficacy of pramipexole for treatment of RLS after a period of six months. RLS patients who responded to pramipexole dihydrochloride monohydrate tablets treatment in a preceding 6-month open label treatment phase (defined as having a CGI-I rating of “very much improved” or “much improved” compared to baseline and an IRLS score of 15 or below) were randomized to receive either continued active treatment (n=78) or placebo (n=69) for 12 weeks. The primary endpoint of this study was time to treatment failure, defined as any worsening on the CGI-I score along with an IRLS Scale total score above 15.
In patients who had responded to 6-month open label treatment with pramipexole dihydrochloride monohydrate tablets, the administration of placebo led to a rapid decline in their overall conditions and return of their RLS symptoms. At the end of the 12-week observation period, 85% of patients treated with placebo had failed treatment, compared to 21% treated with blinded pramipexole, a difference that was highly statistically significant. The majority of treatment failures occurred within 10 days of randomization. For the patients randomized, the distribution of doses was: 7 on 0.125 mg, 44 on 0.25 mg, 47 on 0.5 mg, and 49 on 0.75 mg.
Study 248.520 was a 6-week study, comparing a flexible dose of pramipexole dihydrochloride monohydrate tablets to placebo. In this study, 345 patients were randomized in a 2:1 ratio to pramipexole dihydrochloride monohydrate tablets or placebo. The mean improvement from baseline on the IRLS Scale total score was -12 for pramipexole dihydrochloride monohydrate tablets-treated patients and -6 for placebo-treated patients. The percentage of CGI-I responders was 63% for pramipexole dihydrochloride monohydrate-treated patients and 32% for placebo-treated patients. The between-group differences were statistically significant for both outcome measures. For the patients randomized to pramipexole dihydrochloride monohydrate tablets, the distribution of achieved doses was: 35 on 0.125 mg, 51 on 0.25 mg, 65 on 0.5 mg, and 69 on 0.75 mg.
Study 248.515 was a 3-week study, comparing 4 fixed doses of pramipexole dihydrochloride monohydrate tablets, 0.125 mg, 0.25 mg, 0.5 mg, and 0.75 mg, to placebo. Approximately 20 patients were randomized to each of the 5 dose groups.
The mean improvement from baseline on the IRLS Scale total score and the percentage of CGI-I responders for each of the pramipexole dihydrochloride monohydrate tablets treatment groups compared to placebo are summarized in Table 11. In this study, the 0.125 mg dose group was not significantly different from placebo. On average, the 0.5 mg dose group performed better than the 0.25 mg dose group, but there was no difference between the 0.5 mg and 0.75 mg dose groups.
Table 11: Mean changes from baseline to week 3 in IRLS Score and CGI-I (Study 4)
| Pramipexole dihydrochlo-ride monohydrate tablets 0.125 mg | Pramipexole dihydrochlo-ride monohydrate tablets 0.25 mg | Pramipexole dihydrochlo-ride monohydrate tablets 0.5 mg | Pramipexole dihydrochlo-ride monohydrate tablets 7.5 mg | Pramipexole dihydrochlo-ride monohydrate tablets total | Placebo | |
|---|---|---|---|---|---|---|
| No. of patients | 21 | 22 | 22 | 21 | 86 | 21 |
| IRLS Score | -11.7 | -15.3 | -17.6 | -15.2 | -15.0 | -6.2 |
| CGI-I responders * | 61.9% | 68.2% | 86.4% | 85.7% | 75.6% | 42.9% |
*CGI-I responders = “much improved” and “very much improved”.
No differences in effectiveness based on age or gender were detected. There were too few non-Caucasian patients to evaluate the effect of race.
14.2 Comparative Bioavailability Studies
A randomized, two-treatment, two-period, single-dose, crossover comparative bioavailability study of APO-PRAMIPEXOLE 0.25 mg tablets (Apotex Inc.) with MIRAPEX® 0.25 mg tablets (Boehringer Ingelheim (Canada) Ltd.) was conducted in healthy adult subjects under fasting conditions. Comparative bioavailability data from 16 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Pramipexole (1 x 0.25 mg) Geometric Least Square Mean Arithmetic Mean (CV%) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 5.51 5.64 (21) | 5.40 5.55 (22) | 101.9 | 97.3 – 106.8 |
AUCI (ng·h/mL) | 5.77 5.91 (22) | 5.73 5.88 (22) | 100.7 | 96.3 – 105.3 |
Cmax (ng/mL) | 0.47 0.48 (27) | 0.46 0.47 (25) | 102.3 | 96.8 – 108.1 |
Tmax3 (h) | 2.25 (0.50 – 6.00) | 2.50 (0.75 – 5.00) | ||
| T1/24 (h) | 9.82 (26) | 11.08 (27) | ||
1 APO-PRAMIPEXOLE (pramipexole dihydrochloride) tablets, 0.25 mg (Apotex Inc.) 2 MIRAPEX® (pramipexole dihydrochloride) tablets, 0.25 mg (Boehringer Ingelheim (Canada) Ltd.) 3 Expressed as the median (range) only 4 Expressed as the arithmetic mean (CV%) only | ||||
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute toxicity
The acute toxicity of pramipexole was studied in mice, rats, and dogs following oral and intravenous single doses. Administration of the pramipexole dose was followed by a 14 day observation period. Comparative lethality data are presented in the table below.
TABLE 12: SPECIES COMPARISON OF LD50
| Strain | Initial Group | Route | Doses (mg/kg) | Approximate LD50 (95% Confidence Limits) mg/kg |
|---|---|---|---|---|
| Studies in the Mouse | ||||
| Chbi:NMRI | 5M, 5F | Oral | 1400, 2000 | M, F: 1700 |
| Strain | Initial Group | Route | Doses (mg/kg) | Approximate LD50 (95% Confidence Limits) mg/kg |
|---|---|---|---|---|
| Chbi:NMRI | 5M, 5F | Intravenous | 100, 125, 160, 200 | M: 155 F: 188.3 (151.9-194.9) M, F: 168.8 (150.8-195.2) |
| Chbi:NMRI | 5M, 5F | Intravenous | 0, 70, 100 (in 20% PEG) 100 (in 0.9% saline) | In 20% PEG: M: 94.4 F: 87.9 M, F: 90.6 In 0.9% saline: There were no deaths, therefore no determination could be made |
| Studies in the Rat | ||||
| Chbb:THOM | 5M, 5F | Oral | 100, 200, 200, 400, 560, 800 | M: >800 F: >548.0 M, F: >809.4 |
| Chbb:THOM | 5M, 5F | Intravenous | 100, 140, 140, 180, 225 | M, F: 210 |
| Studies in the Dog | ||||
| Chbi:Beagle | 1M, 1F | Oral | 0.001, 0.01, 0.1, 1.0 | Not determined |
| Chbi:Beagle | 1M, 1F | Intravenous | 0.001, 0.003, 0.005, 0.01 | Not determined |
Clinical symptoms following acute dosing in rats and mice included ataxia, convulsions, dyspnea, tachypnea, reduced motility, increased nervousness or hyperactivity. In dogs, oral and intravenous dosing resulted in frequent and prolonged vomiting.
Long-term toxicity
The effects of long-term administration of pramipexole were evaluated in the rat, minipig, and monkey. Definitive studies have been summarized in Table 13.
Table 13: SUMMARY OF LONG-TERM TOXICITY STUDIES
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results |
|---|---|---|---|---|---|
Rat Crl: (WI) BR | 20 M, 20 F in control, 25 mg/k g groups 10 M, 10 F in other groups | Oral, gavage (in saline) | 0, 0.5, 4, 25 | 13 weeks, with 8 week post-treatment follow-up for controls, 25 mg/kg group | Unscheduled deaths occurred in 3 F controls, 1M, 1F at 4 mg/kg, 1M, 1F at 25 mg/kg, and in one moribund female at 0.5 mg/kg. The incidence and distribution of the unscheduled deaths was not dose or treatment related. Clinical signs included slight sedation in 0.5 mg/kg males and increased spontaneous activity in all other treated groups. Reduced body weight gain and increased water consumption was noted in males at 4 mg/kg, while the females of this group had increased food consumption, reduced blood cholesterol levels, increased ovarian weight, reduced spleen weight, histologically diagnosed increases in the size of corpora lutea and lipid depletion in the adrenal cortex. At 25 mg/kg all changes noted in the 4 mg/kg group occurred. In addition, water consumption was increased in males, with a corresponding increase in urine production. Also noted were a slight, |
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results |
|---|---|---|---|---|---|
reversible, relative rise in granulocytes with a corresponding decrease in lymphocytes in females (week 13); a decrease in serum cholesterol, triglycerides and phospholipids in both sexes, reduced serum fatty acid levels in males. Females also had reduced thymic weight, and retained uterine fluid was noted. There were no oculotoxic changes and no urinalysis changes attributable to treatment. All drug-induced findings were reversed by the end of the 8 week recovery period. The NOEL of pramipexole in rats as defined in this study was 0.5 mg/kg/day. | |||||
Rat Chbb:THO M | 20 M, 20 F | Oral, diet | 0, 0.5, 3, 15 | 52 weeks | There were 6 intercurrent deaths (2 F controls, 2 M at 0.5 mg/kg; 2 M, 1 F at 15 mg/kg) and 2 moribund sacrifices (1 M control, 1M at 15 mg/kg). The three high dose animals died during or after blood sampling. At 0.5 mg/kg, no toxic changes were noted. Pharmacological effects included increased diurnal and nocturnal activity, |
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |
|---|---|---|---|---|---|---|
particularly in females. In females, increased feed intake with reduced body weight gain, slightly reduced serum cholesterol and triglycerides, slightly increased ovarian weight and a relative granulocytosis (neither of which was accompanied by relevant histopathological changes) were recorded. At 3 mg/kg, the same changes were noted, but to a greater degree. Food consumption, reduced body weight gain, slightly reduced triglycerides were also observed in males. In females, slight thrombocytopenia and slight elevated serum GPT, GOT, AP, and urea values were recorded. Ovarian weight was significantly increased, reflecting a mild to marked luteal enlargement seen histologically in 18 of 20 animals. In females only, absolute thymic weight was significantly reduced and adrenal weight nonsignificantly increased, without histological changes. Concurrent with a proliferation of the glandular epithelium in females of the mid and high dose groups, a change of the female-like | ||||||
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |
|---|---|---|---|---|---|---|
tubuloalveolar morphology of the mammary gland to the typical male-like lobuloalveolar or mixed male/female lobuloalveolar/tubuloalveol ar glandular pattern occurred. Secretory activity in the changed glandular pattern was inconspicuous and consistent with the prolactin-inhibiting effects of the compound. These changes are regarded as reflective of a physiological aspect of mammary development attributable to a hormonal imbalance induced by the prolactin-inhibitory effect of pramipexole combined with the prolonged duration of treatment. Mammary glands of the male rats were unaffected. At 15 mg/kg, all changes noted in the 3 mg/kg group were noted, to a more pronounced degree. The exception was increased food consumption in males, which remained comparable to controls in the high dose group. Additional observations in the high dose group included a hemorrhagic vaginal discharge, significantly increased adrenal weight in females; significantly decreased liver | ||||||
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |
|---|---|---|---|---|---|---|
weight (with no accompanying histological changes) and esophageal dilatation/impaction in 2 of 20 males. Histologically, pyometra was recorded at a higher frequency in the 15 mg/kg/day group. Depletion of adrenocortical lipids and/or birefringent substances was diagnosed in a small number of females at 15 mg/kg. Chronic pharmacological examination established an increase in spontaneous activity in all treated animals (particularly marked in the 3 and 15 mg/kg groups) as well as an increase in nocturnal activity at 15 mg/kg. Mean plasma concentrations of pramipexole varied within two orders of magnitude. The dose-dependent increase in plasma concentrations was steeper in males than in females. Plasma levels at weeks 26 and 52 were higher in males than in females at 15 mg/kg/day in spite of the fact that drug-related signs were more marked in females. The majority of findings were dose-related from 0.5 | ||||||
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results |
|---|---|---|---|---|---|
| to 15 mg/kg/day and were consistent with the pharmacological properties of dopamine agonists. Under the conditions of the study, the toxic NOEL was 0.5 mg/kg/day. | |||||
Rat Chbb:THO M | 10M, 10F | Intravenou s | 0, 0.2, 1, 10 | 5 | There were 7 intercurrent deaths - 3 M, 1 F at 0.2 mg/kg; 1 M, 2 F at 10 mg/kg. These deaths were not attributed to treatment with pramipexole. There were no treatment related differences in the incidence of clinical findings, ophthalmology, blood parameters, or urinalysis. Measurement of spontaneous activity at week 3 showed an increase lasting from 4 to 6 hours in low and mid dose animals and from 12 to 15 hours in high dose rats. Food consumption was reduced in rats at 10 mg/kg during the first week of the study. Treated animals showed a tendency to consume more feed. Water consumption was increased at 10 mg/kg. Spleen weight was decreased in males, reaching statistical significance for absolute and relative values only in |
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |||
|---|---|---|---|---|---|---|---|---|
the 1 mg/kg group. Ovarian weight and size were increased and thymus weight was decreased in females at 10 mg/kg. No treatment related histopathological changes were observed. In females at 10 mg/kg, a slight fall in cholesterol levels was noted; in the 10 mg/kg males, reduced triglyceride and potassium values and a slight rise in chloride levels were recorded. Based on the results of this study the toxic NOEL was approximately 1 mg/kg/day. | ||||||||
Minipig Troll | 3M, 3F 6M, 6F in 5 mg/ kg group | Oral, diet | 0, 0.3, 1, 5 | 13 8 week follow-up observatio n | There were no unscheduled deaths during the study. Mild ataxia, tremors, hyperactivity, and piloerection were observed in all treated groups. Behavioural changes noted 1 hour after administration of 0.3 mg/kg or higher doses were considered to be a pharmacodynamic effect, occurring regularly only in the first few weeks of the study and lessening after 2 to 4 weeks. These signs were not dose dependent. | |||
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |
|---|---|---|---|---|---|---|
A stagnation in body weight gain was noted in treated animals up to the 9th week of the study. Although the same amount of food was consumed by the treated minipigs and the controls, body weight gain was clearly reduced. It is doubtful that the substance-induced hyperactivity and increased motility of the animals is a sufficient explanation because the recovery group females did not show a clear increase in body weight gain with the cessation of dosing. The serous atrophy of the fatty tissue of the atrioventricular groove and of the fats cells in the bone marrow detected at autopsy and histopathologically in sows and one male pig is characteristic of animals in a poor nutritional state. Apart from a slight increase in the reticulocyte count in the animals at 5 mg/kg, in week 2, no other treatment-related or histopathological changes were seen. ECGs (weeks 2, 6, 12) revealed a decrease in heart rate at 1 and 3 hours after ingestion of pramipexole. The rates | ||||||
| Strain | Initial Group | Route | Doses (mg/kg/day) | Duration (weeks) | Results | |
|---|---|---|---|---|---|---|
decreased from pretreatment values by 16% to 35% (0.3 mg/kg), 17% to 32% (1 mg/kg) and 12% to 33% (5 mg/kg). These changes were considered to be a pharmacodynamic effect of the compound. Increased locomotion caused by pramipexole lasting for several hours was observed in all treated groups in weeks 4, 8, 10, and 11. Chronic pharmacology examinations (blood pressure and heart rate) of the 0.3 mg/kg supplemental groups (weeks 1, 5, 11) showed a decrease in systolic and diastolic blood pressure. Under the conditions of this study, a NOEL was not established. | ||||||
A delay in sexual development (i.e., preputial separation and vaginal opening) was observed in rats. The relevance for humans is unknown.
Retinopathy In Albino Rats
Pathologic changes (degeneration and loss of photoreceptor cells) were observed in the retina of albino rats in the 2-year carcinogenicity study with pramipexole. These findings were first observed during week 76 and were dose-dependant in animals receiving 2 mg/kg/day (25/50 male rats, 10/50 female rats) and 8 mg/kg/day (44/50 male rats, 37/50 female rats). Plasma AUCs at these doses were 2.5 and 12.5 times the AUC seen in humans at the maximal recommended dose of 4.5 mg per day. Similar findings were not present in either control rats, or in rats receiving 0.3 mg/kg/day of pramipexole (0.3 times the AUC seen in humans at the 4.5 mg per day dose).
No retinal degeneration was seen in the two year carcinogenicity study in mice at doses of 0.3, 2, or 10 mg/kg/day, in the one year drug-in-diet rat study at doses of 0.5, 3, or 15 mg/kg/day, or in any other study in any species.
Studies demonstrated that pramipexole at very high dose (25 mg/kg/day) reduced the rate of disk shedding from the photoreceptor rod cells of the retina in albino rats; this reduction was associated with enhanced sensitivity to the damaging effects of light. In a comparative study, degeneration and loss of photoreceptor cells occurred in albino rats after 13 weeks of treatment with 25 mg/kg/day of pramipexole (54 times the highest clinical dose on an mg/m basis) and constant light (100 lux) but not in Brown-Norway rats exposed to the same dose and higher light intensities (500 lux) (see 7 WARNINGS AND PRECAUTIONS, Retinal Pathology in Albino Rats).
Local tolerance
Pramipexole at a single dose of 100 mg or repeated doses of 0.05% to 0.5% for three days was not irritating to rabbit eyes. Doses of 0.00625% to 0.5% administered to rabbits for four weeks caused mild to moderate increased conjunctival secretion and isolated mild reddening. There was no concentration-effect relationship and findings were fully reversible. No treatment-related histopathological changes of dose-related systemic reactions were observed.
Pramipexole at a single dose of 0.5 g applied occlusively and semi-occlusively to the intact skin of male rabbits was not irritating. Repeated doses of 0.1 g applied to the skin of male rabbits under occlusion for 24-hour periods for five consecutive days was not irritating to intact skin but caused mild, reversible irritation to abraded skin.
A 0.1% injectable solution of pramipexole injected paravenously into the jugular vein was conditionally tolerated by rats. Single intravenous injections of pramipexole 0.1% solution into the marginal vein of the ear were tolerated by rabbits. Single intra-arterial injections of pramipexole into the central artery of the ear were tolerated by rabbits.
A skin sensitization (Maximization Test) study in guinea pigs with pramipexole base resulted in a mild sensitizing potential based on sensitization rates of 25% (first challenge) and 20% (rechallenge). A skin sensitization (Modification of Beuhler Test) study in guinea pigs with pramipexole base as a CPA-patch formulation did not reveal any sensitizing potential.
A 0.1% pramipexole solution for injection added to freshly drawn citrated human blood had no hemolytic effect.
Genotoxicity:
In a standard battery of in vitro and in vivo studies, pramipexole was found to be non-mutagenic and non-clastogenic.
Carcinogenicity:
Two-year carcinogenicity studies have been conducted with pramipexole in mice and rats. In rats, pramipexole was administered in the diet, at doses of 0.3, 2 and 8 mg/kg/day. The highest dose corresponded to 12.5 times the highest recommended clinical dose (1.5 mg t.i.d.) based on comparative AUC values. No significant increases in tumours occurred.
Testicular Leydig cell adenomas were found in male rats as follows: 13 of 50 control group A males, 9 of 60 control group B males, 17 of 50 males given 0.3 mg/kg/day, 22 of 50 males given 2 mg/kg/day, and 22 of 50 males given 8 mg/kg/day. Leydig cell hyperplasia and increased numbers of adenomas are attributed to pramipexole-induced decreases in serum prolactin levels, causing a down-regulation of Leydig cell luteinizing hormone (LH) receptors and a compensatory elevation of LH secretion by the pituitary gland. The endocrine mechanisms believed to be involved in rats are not relevant to humans.
In mice, pramipexole was administered in the diet, at doses of 0.3, 2 and 10 mg/kg/day. The highest dose corresponded to 11 times the highest recommended clinical dose on an mg/m2 basis. No significant increases in tumours occurred.
Pramipexole was not mutagenic in a battery of in vitro and in vivo assays including the Ames assay and the in vivo mouse micronucleus assay.
Mouse
Pramipexole was administered to Chbb:NMRI mice, 50/sex/group for two years at drug in-diet-doses of 0.3, 2, or 10 mg/kg/day. Two control groups received only powdered feed.
Plasma concentrations of pramipexole rose with increasing doses in an almost linear, or more steeply than linear, manner. On average, females had higher plasma levels than males.
No distinct, drug-related clinical effects were noted at 0.3 mg/kg/day, although this group had a tendency to consume less feed than the control groups. In the 2 and 10 mg/kg groups, lower body weights and a tendency for increased food and water consumption were noted. Increased spontaneous activity was noted in females at 2 mg/kg, and in both sexes at 10 mg/kg.
The following non-neoplastic changes were noted: increased incidence of fibro-osseous proliferative lesions in the femurs of treated females, decreased incidence of tubular atrophy in the testes of treated males. Increased hemopoietic activity was noted in the femoral bone marrow of females at 2 and 10 mg/kg.
With the exception of a nonsignificant decrease in hepatocellular adenomas in males in all treated groups, and statistically significant decreases in adrenal cortical adenomas in males at 10 mg/kg and malignant lymphomas in females at 2 and 10 mg/kg, the incidence of neoplastic changes was similar in treated and control animals.
Therefore, under the conditions of the study, no carcinogenic effect of the test compound could be established.
Rat
Pramipexole was administered to Chbb:THOM rats, 50/sex/group, for two years by drug-in-diet, at doses of 0.3, 2, or 8 mg/kg/day. Two control groups received only vehicle (powdered feed).
Plasma concentrations of pramipexole increased almost proportionally with increasing dose.
The incidence of mortality (unscheduled deaths and sacrifices) was similar in the treated and two control groups.
Increased spontaneous activity was observed in females at 8 mg/kg. A dose-related, slight to marked decrease in body weight gain was observed in all treated groups, particularly in females. Food consumption was slightly decreased in males from all treated groups, but was moderately increased in females at 2 and 8 mg/kg.
An increased incidence of the following non-neoplastic changes was noted: Leydig cell hyperplasia in males at 2 and 8 mg/kg; large, prominent corpora lutea in females at 8 mg/kg; chronic suppurative inflammatory lesions and hemorrhages in the uteri of females at 2 and 8 mg/kg; change in normal glandular pattern in the mammary gland parenchyma in females at 2 and 8 mg/kg; retinal degeneration in males and females at 2 and 8 mg/kg; minimal to slight diffuse hepatocellular fatty change in females at 2 and 8 mg/kg. A treatment-related decrease in the incidence of focal/multifocal medullary hyperplasia of the adrenal gland and cystic changes of the mammary gland were observed in females at 2 and 8 mg/kg.
A statistically significant increase in the incidence of Leydig cell adenomas was noted in males at 2 and 8 mg/kg. The following neoplasms were significantly decreased in rats at 2 and 8 mg/kg: mammary gland neoplasia in females, pituitary adenomas in both sexes, total number of primary neoplasms in females. Additionally, a decrease in the incidence of benign adrenal medullary neoplasms was observed in female rats at 0.3, 2, and 8 mg/kg/day.
In conclusion, under the conditions of this study, apart from slight decreases in body weight gain, no drug-related adverse effects, including hyperplastic/neoplastic lesions, were recorded at the lowest dose of 0.3 mg/kg/day. Therefore, the NOAEL was 0.3 mg/kg/day.
Reproductive and Developmental Toxicology
Fertility and early embryonic development
Pramipexole, at a dose of 2.5 mg/kg/day inhibited implantation. This finding is thought to be due to the prolactin lowering effect of pramipexole. Prolactin is necessary for implantation and maintenance of early pregnancy in rats, but not in rabbits and humans. Because of pregnancy disruption and early embryonic loss, the teratogenic potential of pramipexole could not be assessed adequately. In pregnant rabbits which received doses up to 10 mg/kg/day during organogenesis (plasma AUC 71 times that seen in humans at the 1.5 mg t.i.d. dose), there was no evidence of adverse effects on embryo-fetal development. Postnatal growth was inhibited in the offspring of rats treated with a 0.5 mg/kg/day dose of pramipexole during the latter part of pregnancy and throughout lactation.
Groups of 24 male and 24 female Chbb:THOM rats were administered pramipexole in distilled water at doses of 0 (vehicle), 0.1, 0.5, or 2.5 mg/kg/day. Males were treated for 10 weeks prior to mating and throughout copulation; females were treated 2 weeks prior to mating during the mating period, and during the gestation and lactation periods.
No treatment-related effects were observed in adults in the 0.1 mg/kg/day group. Additionally, no treatment-related effects were observed in the offspring in this group.
Rats in the 0.5 mg/kg/day group (particularly females) showed clinical signs of CNS excitation (agitation and constant running lasting 6 to 7 hours). Food consumption, body weight, mating, and pregnancy parameters were not affected. A dose of 2.5 mg/kg/day caused moderate to severe agitation in adults, associated with temporary retardation of body weight and food consumption. Treatment-related irregularities in the estrous cycle and/or the severe agitation observed over the treatment period in the 2.5 mg/kg/day group may have been connected to the longer mating performance and the high percentage (61%) of females which failed to become pregnant in this group. The high percentage of non-pregnant females may also have been due to an inhibition of prolactin secretion by pramipexole since the maintenance of functional corpora lutea and successful implantation are dependent upon prolactin.
In the 0.5 mg/kg group, litter parameters of the Caesarean-section group were unchanged, but in the spontaneous delivery group pup body weight development was delayed. While it was not possible to evaluate litter parameters for the Caesarean-section group at 2.5 mg/kg (only one dam produced living progeny), the few pups from the 2.5 mg/kg spontaneous delivery group weighed less at birth and had an even smaller weight increase during the rearing than the 0.5 mg/kg group. In both groups, a slight delay in opening of the eyes was observed. Effects observed in pups in the 0.5 and 2.5 mg/kg/day groups were believed to result from maternal toxicity.
Under the conditions of this study, pramipexole produced maternal toxicity at doses of 0.5 mg/kg/day and greater. There was no indication of impaired male fertility. No teratogenic effects were seen. Apart from retarded weight gain and a retardation in the maturation parameter ‘opening of the eyes’ in the mid-and high-dose pups, the fertility test on the F1 generation showed no impairments. The maximum no-effect dose was 0.1 mg/kg/day.
Due to the lower conception rate in rats administered 2.5 mg/kg/day in the above study; a second Segment I study was conducted. Pramipexole in distilled water was administered to rats at oral doses of 0 (vehicle) or 2.5 mg/kg/day to groups of 24 males at least 9 weeks before mating and during the mating period, and to groups of 24 females at least 2 weeks before mating and during the mating and gestation period as follows: Group 0 (vehicle control): males and females treated with distilled water; Group 1 (positive control): males and females treated with 2.5 mg/kg/day pramipexole; Group 2: males treated with 2.5 mg/kg/day pramipexole, females with distilled water; and Group 3: males treated with distilled water, females with 2.5 mg/kg/day of pramipexole.
Slight toxic effects were noted in treated animals (temporary reduction in body weight gain in males, body weight loss in females at study initiation accompanied by decreased feed intake followed by overcompensation). Both sexes reacted with moderate to severe agitation, which lasted 8 hours or more after administration.
Although treated and untreated couples mated as expected, the number and percentage of pregnant dams were significantly reduced in treated females regardless of whether or not the male partners had been treated. The estrous cycle of about 50% of treated females was prolonged. Light microscopical examination of ovaries from treatment groups 1 and 3 showed an increase in the number of corpora lutea by 75% and 62.5%, respectively. A slight decrease in number of ovarian follicles (showing all stages of folliculogenesis) was noted. A significant (p <0.001) decrease in prolactin levels in all treated males and in eight out of 10 treated females after the administration of 2.5 mg/kg per day was found. The prolonged estrous cycle, the inhibition of nidation, and the increased number of corpora lutea were regarded as a consequence of the marked reduction in prolactin levels. No evidence of embryo-/fetotoxicity or teratogenicity was noted.
Plasma levels taken two hours after the last administration showed concentrations of pramipexole in the range of 93 to 236 ng/mL (females) and 134 ng/mL (males).
In conclusion, under the conditions of this study, the effect of lowered fertility in females was clearly shown to be a consequence of female rather than male treatment with pramipexole.
Embryofetal development
Groups of 36 female Chbb:THOM rats were administered pramipexole in distilled water at oral doses of 0 (vehicle), 0.1, 0.5 or 1.5 mg/kg/day from days 7 to 16 of gestation.
Treatment-related CNS stimulation and a dose-dependent decrease in food intake was observed at 0.5 and 1.5 mg/kg/day. In the majority of high-dose (1.5 mg/kg/day) dams (approximately 78%), there were early resorptions of the entire litter. All surviving pups developed normally. The embryotoxicity (resorptions) seen in the high-dose group were associated with predominantly pharmacodynamically-induced CNS effects (agitation and increased spontaneous activity) in the dams. Although a dose of 0.5 mg/kg/day also produced CNS symptoms in the dams, it did not cause embryo toxic or fetotoxic effects in the offspring. No teratogenicity was observed up to and including the high dose of 1.5 mg/kg/day.
Under the conditions of this study, the NOAEL for maternal toxicity was 0.1 mg/kg/day, the NOAEL for embryo-fetal toxicity was 0.5 mg/kg/day, and the teratogenic NOAEL was 1.5 mg/kg/day.
Groups of 18 mated female Chbb:HM rabbits were administered pramipexole in distilled water at oral doses of 0 (vehicle), 0.1, 1, or 10 mg/kg/day from day 6 to 18 of gestation. Fetuses were delivered by C-section on day 29.
Reversible excitation and restlessness after 3 to 4 days of treatment were observed at 10 mg/kg/day. Maternal toxicity was observed at 10 mg/kg per day (temporary dose-dependent weight loss or retarded weight gains, one intercurrent death after the third dose of 10 mg/kg probably due to shock-like cardiovascular collapse). Embryo-/fetotoxicity or teratogenicity was not observed.
Under the conditions of this study, the NOAEL for maternal toxicity was 1 mg/kg/day and the embryo-/fetotoxic and teratogenic NOAEL was 10 mg/kg/day.
Peri-postnatal development
Groups of 24 pregnant Chbb:THOM rats were administered pramipexole in distilled water at oral doses of 0 (vehicle), 0.1, 0.5, or 1.5 mg/kg/day from day 16 of gestation through day 21 of parturition.
The low dose of 0.1 mg/kg/day was well tolerated. Doses of 0.5 and 1.5 mg/kg/day caused considerable agitation and hyperactivity, particularly in lactating rats. Slight maternal toxicity (decreased food consumption) was observed in the 1.5 mg/kg/day dose group. No effects on the duration of pregnancy were observed at any dose.
In the 3-week rearing phase, during which dams in the 0.5 and 1.5 mg/kg/day groups showed signs of great agitation, the body weight increase of pups in those groups was less than that of the controls, perhaps due to insufficient opportunity to suckle. There was no increase in pup mortality, and no fetotoxicity was observed.
The physiological behaviour of the pups during the rearing period and the marginal differences between a few behavioural and developmental parameters in the 0.5 and 1.5 mg/kg/day dose groups, show that despite the great state of excitement in the dams, the vast majority of pups developed normally. Only body weight, which was less (to a dose-dependent degree) than that of control animals, had not recuperated by the time the offspring reached sexual maturity). While the F1 females were lighter, there was no biologically relevant effect on mating and gestational parameters.
Under the conditions of this study the NOEL for maternal toxicity and fetal development was 0.1 mg/kg/day.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. MIRAPEX® (Pramipexole Dihydrochloride Monohydrate Tablets, 0.125 mg, 0.25 mg), submission control 281270, Product Monograph, Boehringer Ingelheim (Canada) Ltd. (MAR 20, 2024)