


Product Monograph - Apo-Triazide
Recent Major Label Changes
| 2026-08 |
|---|---|
| 2026-08 |
| 2026-08 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes .................................................................................................. 2
Table of Contents .................................................................................................................. 2
Part 1: Healthcare Professional Information........................................................................... 5
- 1.
Indications ...................................................................................................................... 5
1.1. Pediatrics .......................................................................................................................... 5
1.2. Geriatrics .......................................................................................................................... 5
- 2. Contraindications .....................................................................................................................5
- 3. Serious Warnings and Precautions Box ..................................................................................6
- 4.
Dosage and Administration .....................................................................................................6
4.1. Dosing Considerations ...................................................................................................... 6
4.2. Recommended Dose and Dosage Adjustment ................................................................ 6
4.4. Administration .................................................................................................................. 6
4.5. Missed Dose ..................................................................................................................... 7
- 5. Overdose ..................................................................................................................................7
- 6. Dosage Forms, Strengths, Composition, and Packaging ........................................................7
- 7.
Warnings and Precautions .......................................................................................................7
General ....................................................................................................................................... 8
Carcinogenesis and Mutagenesis ............................................................................................... 8
Driving and Operating Machinery .............................................................................................. 8
Endocrine and Metabolism ........................................................................................................ 8
Hematologic ............................................................................................................................. 10
Hepatic/Biliary/Pancreatic ....................................................................................................... 10
Immune .................................................................................................................................... 10
Ophthalmologic ........................................................................................................................ 10
Perioperative Considerations ................................................................................................... 11
Renal ........................................................................................................................................ 11
Respiratory ............................................................................................................................... 11
Sensitivity/Resistance .............................................................................................................. 11
Skin ........................................................................................................................................ 12
7.1. Special Populations ........................................................................................................ 12
7.1.1. Pregnancy ....................................................................................................................... 12
7.1.2. Breastfeeding ................................................................................................................. 12
7.1.3. Pediatrics ........................................................................................................................ 12
7.1.4. Geriatrics ........................................................................................................................ 12
- 8.
Adverse Reactions .................................................................................................................. 12
8.1. Adverse Reaction Overview ........................................................................................... 12
8.2. Clinical Trial Adverse Reactions ...................................................................................... 12
8.5. Post-Market Adverse Reactions ..................................................................................... 13
- 9.
Drug Interactions ................................................................................................................... 14
9.4. Drug-Drug Interactions ................................................................................................... 14
9.5. Drug-Food Interactions .................................................................................................. 17
9.6. Drug-Herb Interactions .................................................................................................. 17
9.7. Drug-Laboratory Test Interactions ................................................................................. 17
- 10.
Clinical Pharmacology ............................................................................................................ 17
10.1. Mechanism of Action ..................................................................................................... 17
10.2. Pharmacodynamics ........................................................................................................ 18
10.3. Pharmacokinetics ........................................................................................................... 18
- 11. Storage, Stability, and Disposal ............................................................................................. 19
Part 2: Scientific Information ........................................................................................................ 20
- 13. Pharmaceutical Information .................................................................................................. 20
- 14.
Clinical Trials........................................................................................................................... 21
14.2. Comparative Bioavailability Studies ............................................................................... 21
- 15. Microbiology .......................................................................................................................... 21
- 16. Non-Clinical Toxicology .......................................................................................................... 21
Patient Medication Information ................................................................................................... 24
Part 1: Healthcare Professional Information
1. Indications
APO-TRIAZIDE (Triamterene and Hydrochlorothiazide) is indicated in the maintenance therapy of:
- Patients with edema associated with congestive heart failure, hepatic cirrhosis, and nephrotic syndrome; also in steroid induced edema and idiopathic edema.
- Patients with mild to moderate hypertension in those patients who have developed hypokalemia while on thiazide-like diuretics alone, and in those patients in whom potassium depletion is considered especially dangerous (e.g. digitalized patients). Medical opinion is not unanimous regarding the incidence and/or clinical significance of hypokalemia occurring among hypertensive patients treated with thiazide-like diuretics alone, and concerning the use of potassium-sparing combinations as routine therapy in hypertension.
Fixed-dose combination drugs are not indicated for initial therapy. Patients should be titrated on the individual drugs. If the fixed combination represents the dosage so determined, its use may be more convenient in patient management. If during maintenance therapy dosage adjustment is necessary it is advisable to use the individual drugs.
1.1. Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of APO-TRIAZIDE in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3. Pediatrics).
1.2. Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (see 3. Serious Warnings and Precautions Box).
2. Contraindications
APO-TRIAZIDE is contraindicated in:
- Patients with pre-existing elevated serum potassium, or in patients who develop hyperkalemia while on the drug.
- Patients with anuria, severe or progressive renal dysfunction, including oliguria and progressively increasing azotemia.
- Patients with severe or progressive hepatic dysfunction as it contraindicates further use of APO-TRIAZIDE.
- Patients who are hypersensitive to triamterene, hydrochlorothiazide, or other sulfonamide-derived drugs (see 6. Dosage Forms, Strengths, Composition, and Packaging).
3. Serious Warnings and Precautions Box
|
|---|
4. Dosage and Administration
4.1. Dosing Considerations
Dosage must be determined for individual patients by titration of each component separately. Where the fixed combination in APO-TRIAZIDE provides the dosage so determined, APO-TRIAZIDE may be used for maintenance therapy. If during maintenance therapy dosage adjustment is necessary, it is advisable to use the individual drugs.
4.2. Recommended Dose and Dosage Adjustment
- Edema
The usual dosage is one tablet twice daily after meals. When dry weight is reached, one tablet daily will usually suffice. In some patients, one tablet every other day may be indicated.
- Hypertension
The usual dosage is one tablet twice daily after meals. Dosage may be increased or decreased according to patient's need. If two or more tablets per day are needed they should be given in divided doses. Maximum daily dosage should not exceed four tablets (200 mg triamterene and 100 mg hydrochlorothiazide), and at this dosage the incidence of adverse effects may increase.
- Drug discontinuation
If a diagnosis of acute respiratory distress syndrome (ARDS) is suspected, APO-TRIAZIDE should be withdrawn and the appropriate treatment given.
4.4. Administration
Take APO-TRIAZIDE exactly as prescribed. It is recommended to take your dose at about
- the same time every day.
- APO-TRIAZIDE should be taken after an adequate meal.
4.5. Missed Dose
If the patient misses a dose, inform the patient to skip the missed dose and take the next dose at the regular dosing schedule.
5. Overdose
Electrolyte imbalance is the major concern (see 7. Warnings and Precautions, Endocrine and Metabolism section). Symptoms reported include: polyuria, nausea, vomiting, weakness, lassitude, fever, flushed face, and hyperactive deep tendon reflexes. If hypotension occurs, it may be treated with pressor agents such as levarterenol to maintain blood pressure. Carefully evaluate the electrolyte pattern and fluid balance. Induce immediate evacuation of the stomach through emesis or gastric lavage. There is no specific antidote.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
- 6. Dosage Forms, Strengths, Composition, and Packaging
Table 1 – Dosage Forms, Strengths, and Composition
Description
Each light orange, round, flat-faced, bevelled edge tablet, scored and engraved with “APO” over “50-25” on one side, other side plain, contains: 50 mg triamterene and 25 mg hydrochlorothiazide.
Bottles of 100, 1000, and 5000 tablets.
7. Warnings and Precautions
| Route of Administration | Dosage Form/ Strength/Composition | Non-Medicinal Ingredients |
| Oral | Tablet; 50 mg of Triamterene and 25 mg of Hydrochlorothiazide | colloidal silicon dioxide, croscarmellose sodium, lactose monohydrate, magnesium stearate and sunset yellow aluminium lake 40 %. |
See 3 Serious Warnings and Precautions Box.
General
Potassium supplementation in the form of medication should not be used routinely in conjunction with APO-TRIAZIDE since hyperkalemia may result. Abnormal elevation of serum potassium, although uncommon, is potentially the most serious electrolyte disturbance.
Combination therapy with other potassium-conserving agents is potentially hazardous, since both can cause potassium retention and, in some cases, hyperkalemia. Such combination therapy should not be used routinely. If it is deemed essential the patient must be under close supervision and serum potassium levels determined frequently.
Carcinogenesis and Mutagenesis
Non-melanoma skin cancer: An increased risk of non-melanoma skin cancer (NMSC) [basal cell carcinoma (BCC) and squamous cell carcinoma (SCC) of the skin] after hydrochlorothiazide therapy was reported in some epidemiological studies. The risk may be higher with increasing cumulative use (see 8. Adverse Reactions, 8.5. Post-Market Adverse Reactions). The photosensitizing action of hydrochlorothiazide may be a possible mechanism for NMSC (see 16. Non-Clinical Toxicology, Carcinogenicity, Hydrochlorothiazide).
Patients taking hydrochlorothiazide should be informed of the potential risk of NMSC. They should be advised to regularly check their skin for new lesions as well as changes to existing ones, and to promptly report any suspicious skin lesions. Patients should also be advised to limit exposure to sunlight, to avoid the use of indoor tanning equipment, and to use adequate protection (e.g. a broad spectrum sunscreen with a SPF of 30 or higher, clothing, and a hat) when exposed to sunlight or UV light to minimize the risk of skin cancer.
Alternatives to hydrochlorothiazide may be considered for patients who are at a particularly high risk for NMSC (e.g., light coloured skin, known personal or family history of skin cancer, ongoing immunosuppressive therapy, etc.) (see 8. Adverse Reactions, 8.5. Post-Market Adverse Reactions).
Driving and Operating Machinery
Before you perform tasks which may require special attention, wait until you know how you respond to APO-TRIAZIDE. Dizziness, lightheadedness, or fainting can especially occur after the first dose and when the dose is increased.
Endocrine and Metabolism
Careful checks should be kept for signs of fluid or electrolyte imbalance (hyperkalemia, hyponatremia, hypokalemia and hypochloremic alkalosis). Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively or receiving parenteral fluids.
Because of the potassium-sparing characteristic of triamterene, hypokalemia occurs less frequently with APO-TRIAZIDE than with thiazides alone. The effects of digitalis on the heart may be exaggerated in patients with hypokalemia and signs of digitalis intoxication may be seen at doses previously tolerated.
Triamterene may cause a decreasing alkali reserve with the possibility of metabolic acidosis.
Hyperkalemia: When abnormal, the ECG in hyperkalemia is characterized primarily by tall, peaked T waves or elevations from previous tracings. There may also be lowering of the R wave and increased depth of the S wave, widening or disappearance of the P wave, progressive widening of the QRS complex, prolongation of the PR interval, and ST depression.
If hyperkalemia develops, discontinue APO-TRIAZIDE, substitute the thiazide alone and restrict dietary potassium intake. When indicated by the clinical situation, excess potassium may be removed by dialysis or oral or rectal administration of sodium polystyrene sulfonate. Infusion of glucose and insulin have also been used to treat hyperkalemia.
Electrolyte Imbalance and BUN Increases: Dilutional hyponatremia may occur in edematous patients in hot weather. Appropriate therapy is water restriction rather than administration of salt except in rare instances when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Any chloride deficit is generally mild and usually does not require specific treatment. A chloride deficit may be corrected by the use of ammonium chloride (except in patients with hepatic disease) and largely prevented by a near normal salt intake.
Increases in urea nitrogen level and/or creatinine level have been reported. This apparently is secondary to a reversible reduction of glomerular filtration rate or a depletion of intravascular fluid volume (prerenal azotemia). Levels usually return to normal when APO-TRIAZIDE is discontinued. Careful monitoring of BUN or serum creatinine levels is important when administering APO-TRIAZIDE. If azotemia increases discontinue APO-TRIAZIDE (see 2. Contraindications).
Diabetes Mellitus: Thiazides may cause hyperglycemia and glycosuria and may alter insulin requirements in diabetics.
Other Precautions: Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Calcium excretion is decreased by thiazides.
Pathological changes in the parathyroid glands with hypercalcemia and hypophosphatemia have been observed in a few patients on prolonged thiazide therapy. The common complications of hyperparathyroidism such as renal lithiasis, bone resorption, and peptic ulceration have not been seen. Thiazides should be discontinued before carrying out tests for parathyroid function.
Hyperuricemia may occur or gout may be precipitated in certain patients receiving thiazide therapy.
Hematologic
Patients should be observed regularly for the possible occurrence of blood dyscrasias, or other idiosyncratic reactions. There have been reports of blood dyscrasias in patients receiving triamterene. Leukopenia, thrombocytopenia, agranulocytosis, and aplastic anemia have been reported with the thiazides.
Hepatic/Biliary/Pancreatic
Patients should be observed regularly for the possible occurrence of liver damage.
Cirrhotics with splenomegaly may have marked variations in their blood pictures - including thrombocyte and leukocyte levels – which are not related to drug therapy. Since the triamterene component of APO-TRIAZIDE is a weak folic acid antagonist, it may contribute to the appearance of megaloblastosis in cases where folic acid stores are depleted. Periodic blood studies in these patients are recommended.
APO-TRIAZIDE should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma.
Thiazides can precipitate hepatic coma in patients with severe liver disease. Potassium depletion induced by the thiazide may be important in this connection. Administer APO-TRIAZIDE cautiously and be alert for such early signs of impending coma as confusion, drowsiness and tremor: if mental confusion increases discontinue APO-TRIAZIDE for a few days. Attention must be given to other factors that may precipitate hepatic coma, such as blood in the gastrointestinal tract or pre-existing potassium depletion.
Immune
The possibility of exacerbation or activation of systemic lupus erythmatosus have been reported.
Ophthalmologic
Choroidal Effusion, Acute Myopia and Secondary Angle-Closure Glaucoma related to Hydrochlorothiazide: Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in choroidal effusion, acute transient myopia and/or acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity, blurred vision or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma can lead to permanent vision loss.
The primary treatment is to discontinue hydrochlorothiazide as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Perioperative Considerations
The antihypertensive effect of APO-TRIAZIDE may be enhanced in the post-sympathectomy patient.
Renal
Since triamterene has been found in renal stones, this should be taken into consideration before APO-TRIAZIDE is administered to patients who have a history of renal stones.
Respiratory
Acute Respiratory Toxicity: Very rare severe cases of acute respiratory toxicity, including acute respiratory distress syndrome (ARDS) have been reported after taking hydrochlorothiazide. Pulmonary edema typically develops within minutes to hours after hydrochlorothiazide intake. At the onset, symptoms include dyspnea, fever, pulmonary deterioration and hypotension. Hydrochlorothiazide should not be administered to patients who previously experienced ARDS following hydrochlorothiazide intake.
Sensitivity/Resistance
Sensitivity reactions to thiazides may occur in patients with or without a history of allergy or bronchial asthma.
Skin
Photosensitivity: Photosensitivity reactions have been reported with the use of thiazide diuretics. If photosensitivity reactions occur during treatment with hydrochlorothiazide-containing drugs, treatment should be stopped.
7.1. Special Populations
7.1.1. Pregnancy
Thiazides cross the placental barrier and appear in cord blood. Triamterene has been shown to do the same in ewes and this may occur in humans. The use of APO-TRIAZIDE in women who are or may become pregnant requires that the anticipated benefits be weighed against possible risks to the fetus. Hazards include fetal or neonatal jaundice, thrombocytopenia and possibly other adverse reactions which have occurred in the adult.
7.1.2. Breastfeeding
Thiazides appear in breast milk and triamterene appears in cow's milk. APO-TRIAZIDE should be discontinued or the patient should stop nursing.
7.1.3. Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of APO-TRIAZIDE in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4. Geriatrics
Geriatrics (>65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness (See 3 Serious Warnings and Precautions Box).
8. Adverse Reactions
8.1. Adverse Reaction Overview
Hyperkalemia has been reported (overall incidence less than 8%) and in some cases has been associated with cardiac irregularities. Hyperkalemia is more likely to occur in patients who are seriously ill, have known renal impairment, or in elderly (incidence approximately 12%) or diabetic patients with confirmed or suspected renal insufficiency. Fatalities have been reported in such patients. All patients on APO-TRIAZIDE should be monitored carefully for clinical laboratory and electrocardiographic evidence of hyperkalemia and for acidosis.
8.2. Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
The following adverse reactions have been associated with the use of thiazide diuretics and/or triamterene:
Cardiovascular: Orthostatic hypotension.
Central Nervous System: Dizziness, vertigo, paresthesias, headache, xanthopsia.
Dermatologic - Hypersensitivity: Purpura, photosensitivity, rash, urticaria, necrotizing angiitis (vasculitis, cutaneous vasculitis), fever, respiratory distress including pneumonitis, anaphylactic reactions.
Electrolyte Imbalance: (See 7. Warnings and Precautions, Endocrine and Metabolism).
Gastrointestinal: Dry mouth, anorexia, gastric irritation, nausea, vomiting, cramps, diarrhea, constipation, jaundice (intrahepatic cholestatic), pancreatitis, sialadenitis.
Note: Symptoms of nausea and vomiting can also indicate electrolyte imbalance.
Hematologic: Leukopenia, thrombocytopenia, agranulocytosis, aplastic anemia.
Miscellaneous: Hyperglycemia, glycosuria, hyperuricemia, muscle spasm, weakness, restlessness, transient blurred vision.
Newborn, whose mothers had received thiazides during pregnancy, in rare instances have developed thrombocytopenia or pancreatitis.
Renal: Triamterene (and its metabolite p-hydroxytriamterene) have been found in renal stones in association with the usual components. Rare cases of interstitial nephritis have been reported.
8.5. Post-Market Adverse Reactions
Acute respiratory distress syndrome (ARDS) (very rare)
Eye disorders – choroidal effusion, acute myopia, acute angle-closure glaucoma (frequency unknown).
Non-melanoma skin cancer
Some pharmacoepidemiological studies have suggested a higher risk of squamous cell carcinoma (SCC) and basal cell carcinoma (BCC) of the skin with increasing use of hydrochlorothiazide. A systematic review and meta-analysis undertaken by Health Canada suggested that, with important uncertainty, the use of hydrochlorothiazide for several years (>3 years) could lead to:
- 122 additional cases (95% CI, from 112 to 133 additional cases) of SCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 3 observational studies);
- 31 additional cases (95% CI, from 24 to 37 additional cases) of BCC per 1000 treated patients compared with non-use of hydrochlorothiazide (meta-analysis of 2 observational studies).
9. Drug Interactions
9.4. Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 – Established or Potential Drug-Drug Interactions
| Proper/ Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Proper/ Common name | Source of Evidence | Effect | Clinical comment |
| Proper/ Common name | Source of Evidence | Effect | Clinical comment |
| Proper/ Common name | Source of Evidence | Effect | Clinical comment |
| Alcohol, barbiturates, or narcotics | C | Potentiation of orthostatic hypotension may occur. | Avoid alcohol, barbiturates or narcotics, especially with initiation of therapy. |
| Amphotericin B | T | Amphotericin B increases the risk of hypokalemia induced by thiazide diuretics. | Monitor serum potassium level. |
| Antidiabetic agents (e.g. insulin and oral hypoglycemic agents) | CT | Thiazide-induced hyperglycemia may compromise blood sugar control. Depletion of serum potassium augments glucose intolerance. | Monitor glycemic control, supplement potassium if necessary, to maintain appropriate serum potassium levels, and adjust diabetes medications as required. |
| Antihypertensive drugs | CT | Hydrochlorothiazide may potentiate the action of other antihypertensive drugs (e.g. guanethidine, methyldopa, beta-blockers, vasodilators, calcium channel blockers, ACEI, ARB, and direct renin inhibitors). | |
| Antineoplastic drugs, including cyclophosphamide and methotrexate | C | Concomitant use of thiazide diuretics may reduce renal excretion of cytotoxic agents and enhance their myelosuppressive effects. | Hematological status should be closely monitored in patients receiving this combination. Dose adjustment of cytotoxic agents may be required. |
| Bile acid sequestrants, e.g. cholestyramine | CT | Bile acid sequestrants bind thiazide diuretics in the gut and impair gastrointestinal absorption by 43-85%. Administration of thiazide 4 hours after a bile acid sequestrant reduced absorption of hydrochlorothiazide by 30-35%. | Give thiazide 2-4 hours before or 6 hours after the bile acid sequestrant. Maintain a consistent sequence of administration. Monitor blood pressure, and increase dose of thiazide, if necessary. |
| Calcium and vitamin D supplements | C | Thiazides decrease renal excretion of calcium and increase calcium release from bone. | Monitor serum calcium, especially with concomitant use of high doses of calcium supplements. Dose reduction or withdrawal of calcium and/or vitamin D supplements may be necessary. |
| Carbamazepine | C | Carbamazepine may cause clinically significant hyponatremia. Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Corticosteroids, and adrenocorticotropic hormone (ACTH) | T | Intensified electrolyte depletion, particularly hypokalemia, may occur. | Monitor serum potassium, and adjust medications, as required. |
| Digoxin | CT | Thiazide-induced electrolyte disturbances, i.e. hypokalemia, hypomagnesemia, increase the risk of digoxin toxicity, | Concomitant administration of hydrochlorothiazide and digoxin requires caution. Monitor electrolytes and digoxin levels closely. |
| which may lead to fatal arrhythmic events. | Supplement potassium or adjust doses of digoxin or thiazide, as required. | ||
| Drugs that alter GI motility, i.e., anti-cholinergic agents, such as atropine and prokinetic agents, such as metoclopramide, domperidone | CT, T | Bioavailability of thiazide diuretics may be increased by anticholinergic agents due to a decrease in gastrointestinal motility and gastric emptying. Conversely, prokinetic drugs may decrease the bioavailability of thiazide diuretics. | Dose adjustment of thiazide may be required. |
| Gout medications (allopurinol, uricosurics, xanthine oxidase inhibitors) | T, RCS | Thiazide-induced hyperuricemia may compromise control of gout by allopurinol and probenecid. The co-administration of hydrochlorothiazide and allopurinol may increase the incidence of hypersensitivity reactions to allopurinol. | Dosage adjustment of gout medications may be required. |
| Lithium | CT | Thiazide diuretics reduce the renal clearance of lithium and add a high risk of lithium toxicity. | Concomitant use of thiazide diuretics with lithium is generally not recommended. If such use is deemed necessary, reduce lithium dose by 50% and monitor lithium levels closely. |
| Nonsteroidal anti-inflammatory drugs (NSAID) | CT | NSAID-related retention of sodium and water antagonises the diuretic and antihypertensive effects of thiazides. NSAID-induced inhibition of renal prostaglandins leading to decreases of renal blood flow, along | If combination use is necessary, monitor renal function, serum potassium, and blood pressure closely. Dose adjustments may be required. |
| with thiazide-induced decreases in GFR may lead to acute renal failure. Patients with heart failure may be at particular risk | |||
| Selective serotonin reuptake inhibitors (SSRIs, e.g. citalopram, escitalopram, sertraline) | T, C | Concomitant use with thiazide diuretics may potentiate hyponatremia. | Monitor serum sodium levels. Use with caution. |
| Skeletal muscle relaxants of the curare family, e.g., tubocurare | C | Thiazide drugs may increase the responsiveness of some skeletal muscle relaxants, such as curare derivatives | |
| Topiramate | CT | Additive hypokalemia. Possible thiazide-induced increase in topiramate serum concentrations. | Monitor serum potassium and topiramate levels. Use potassium supplements, or adjust topiramate dose as necessary. |
Legend: C = Case Study; RCS = Retrospective Cohort Study; CT = Clinical Trial; T = Theoretical
9.5. Drug-Food Interactions
Interactions with food have not been established.
9.6. Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7. Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10. Clinical Pharmacology
10.1. Mechanism of Action
APO-TRIAZIDE is a combination of two diuretics with different but complimentary modes of action. The natriuretic, diuretic and antihypertensive activity of the thiazide is supplemented by the mild diuretic and potassium-conserving action of triamterene. The combination reduces the risk of hypokalemia and of acid-base imbalance seen sometimes with the use of hydrochlorothiazide alone.
Hydrochlorothiazide
Hydrochlorothiazide is a diuretic and antihypertensive agent. It affects the renal tubular mechanism of electrolyte reabsorption. Hydrochlorothiazide increases excretion of sodium and chloride in approximately equivalent amounts, and may cause a simultaneous, usually minimal, loss of bicarbonate. Natriuresis is usually accompanied by loss of potassium.
Triamterene
Triamterene inhibits the reabsorption of sodium ions in exchange for potassium and hydrogen ions at that segment of the distal tubule under the control of adrenal mineralocorticoids. Triamterene acts directly on tubular transport and is independent of aldosterone. By inhibiting the ion exchange mechanism of the distal tubule triamterene reduces the excess loss of potassium, hydrogen and chloride ions induced by hydrochlorothiazide. Triamterene alone has little or no antihypertensive effect.
10.2. Pharmacodynamics
Hydrochlorothiazide
Hydrochlorothiazide is a diuretic and antihypertensive agent. It inhibits the reabsorption of sodium and chloride in the distal segment and causes a simultaneous usually minimal loss of bicarbonate. Hydrochlorothiazide decreases the renal excretion of calcium, presumably by a direct action on renal transport. Magnesium excretion is increased.
Triamterene
Triamterene inhibits the reabsorption of sodium ions in exchange for potassium and hydrogen ions in the distal renal tubule through a direct effect and not by competitive aldosterone antagonism. The degree of natriuresis and diuresis produced by triamterene alone is limited; it has an additive diuretic effect when used with a thiazide diuretic. Triamterene has no significant pharmacological action other than those on the kidney.
10.3. Pharmacokinetics
Absorption
Hydrochlorothiazide: Hydrochlorothiazide is absorbed from gastrointestinal tract relatively rapidly since a demonstrable diuretic effect is seen within one hour and reaches a peak effect in about 4 hours. Its action persists for approximately 6 to 12 hours.
Triamterene: Triamterene is rapidly absorbed from the gastrointestinal tract but to a variable extent (30 to 70% of the oral dose). It is excreted in the urine with a peak in renal excretion within 1 to 2 hours after oral ingestion. Diuretic effect following a single dose is evident within 2 to 4 hours and tapers off 7 to 9 hours after administration.
Distribution
Triamterene: The peak plasma concentration of triamterene is reached 2 to 4 hours after an oral dose and the half-life of the drug in plasma ranges from 1.5 to 2 hours. Approximately 50% of triamterene is bound to human plasma protein.
Elimination
Hydrochlorothiazide: Hydrochlorothiazide is eliminated rapidly by the kidney.
Triamterene: Triamterene and its metabolites are excreted by the kidney by filtration and tubular secretion. The peak in triamterene renal excretion occurs 1 to 2 hours after dosing. About 20% of an oral dose appears unchanged in the urine, 70% as the sulphate ester of hydroxytriamterene and 10% as free hydroxytriamterene and triamterene glucuronide. Hydroxytriamterene has diuretic activity.
- 11. Storage, Stability, and Disposal
Store at room temperature 15°C-30°C.
Keep out of reach and sight of children.
Part 2: Scientific Information
13. Pharmaceutical Information
Hydrochlorothiazide
Non-proprietary name of the drug substance: Hydrochlorothiazide
Chemical name: 6-Chloro-3,4-dihydro-2H-l,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide
Molecular formula and Molecular mass: C7H8ClN3O4S2 and 297.72 g/mol
Structural formula:
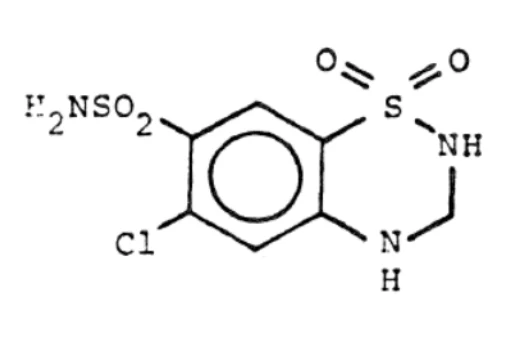
Physicochemical properties: A white or almost white crystalline compound with a slightly bitter taste, almost insoluble in water.
Triamterene
Non-proprietary name of the drug substance: Triamterene
Chemical name: 2, 4, 7-triamino-6-phenylpteridine
Molecular formula and Molecular mass: C12H11N7 and 253.3 g/mol
Structural formula:
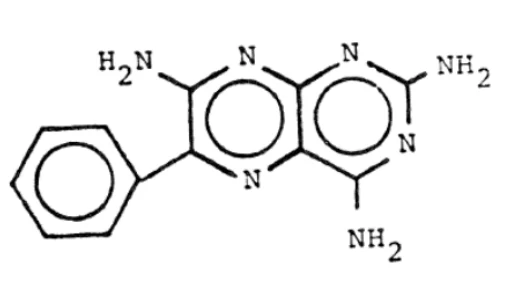
Physicochemical properties: A yellow odourless crystalline compound, tasteless at first with a slightly bitter aftertaste; practically insoluble in water, or chloroform; unstable to light.
14. Clinical Trials
14.2. Comparative Bioavailability Studies
A single dose comparative oral bioavailability study of APO-TRIAZIDE and Dyazide tablets was performed on 18 normal male volunteers. The dose administered was two tablets, that is 100 mg triamterene and 50 mg hydrochlorothiazide. The results can be summarized as follows:
Triamterene
APO-TRIAZIDE
Dyazide
AUC0-24 hrs (ng•hrs/mL)
476
474
Cmax (ng/mL)
143
140
Tmax (hrs)
0.9
1.1
T 1/2 (hrs)
4.9
4.9
Hydrochlorothiazide
APO-TRIAZIDE
Dyazide
AUC0-24 hrs (ng•hrs/mL)
1708
1736
Cmax (ng/mL)
283
276
Tmax (hrs)
2.1
2.1
T 1/2 (hrs)
6.0
6.0
15. Microbiology
No microbiological information is required for this drug product.
16. Non-Clinical Toxicology
General Toxicology
Hydrochlorothiazide
In rats, the oral LD50's were greater than 2750 mg/kg.
Triamterene
The oral LD50 values for triamterene were found to be:
Mouse: 490 mg/kg (95% C.L. 398 to 603 mg/kg)
Rat: 1600 mg/kg (95% C.L. 1409 to 1817 mg/kg)
Subacute and Chronic Toxicity
Combination: Triamterene and Hydrochlorothiazide
Groups of 4 to 6 dogs were orally administered a 1:1 combination of triamterene and hydrochlorothiazide at dose levels of 0, 2, 4 and 15 mg/kg/day of each component for 15 weeks. Elevations of serum alkaline phosphatase of borderline significance and sharp increases in SGPT were seen in the high dose group at 10 weeks with a return to normal at 15 weeks.
Groups of rats were orally administered triamterene-hydrochlorothiazide (1:1) in increasing doses to a maximum of 500 mg/kg/day (each ingredient) for 27 days. Male rats and the surviving female rats (5 of 10) at the maximum dose had enlarged kidneys and a characteristic nephropathy varying from slight to severe.
Dogs administered 50 mg/kg/day (each ingredient) triamterene hydrochlorothiazide (1:1) for 6 days exhibited anorexia, bloody diarrhea mixed with mucous and granular yellow material in the feces. When the dose was increased to 200 mg/kg/day (each component) three of six dogs had elevated SGPT and four of six had slightly elevated serum alkaline phosphatase on day 12, and on day 25 exhibited dyspnea, mild convulsions, prostration and death. Drug-related toxic nephropathy was clearly demonstrated.
Genotoxicity
Hydrochlorothiazide
The mutagenic potential was assessed in a series of in vitro and in vivo test systems. While some positive results were obtained in vitro, all in vivo studies provided negative results. Hydrochlorothiazide enhanced the UVA-induced formation of pyrimidine dimers and in the skin of mice following oral treatment. It is therefore concluded that although there is no relevant mutagenic potential in vivo, hydrochlorothiazide could enhance the genotoxic effects of UVA light. This mechanism of photosensitization could be associated with a higher risk for non-melanoma skin cancer.
Carcinogenicity
Hydrochlorothiazide
According to the experimental data available, hydrochlorothiazide revealed inconsistent evidence of carcinogenic activity in rats and mice, with conflicting evidence of hepatic adenoma in male mice at the highest dose and adrenal pheocytochroma in one rat study but not in another. Current evidence is inadequate to draw a clear conclusion for a carcinogenic effect of hydrochlorothiazide in animals.
Reproductive and developmental toxicology
A reproductive study in 3 groups of 40 male and female rats given a 2:1 combination of triamterene and hydrochlorothiazide in food for 60 days prior to mating and through two litters was performed. One group was a control, the second received 9 mg/kg/day of the combination and a third group was started on 30 mg/kg/day but because of weight loss this was lowered to 15 mg/kg/day on day 5 and on day 52 to 12 mg/kg/day and kept there throughout the study. Mortality among the parent rats was limited to 1 low dose female who died of dystocia. In the first breeding period the live birth index and viability index were similar in all 3 groups. Litter size, birth weight and mean weight of progeny at 3 weeks of age did not differ significantly. Similar results were found in the second breeding period although 3 congenital anomalies (hydrops) were noted, one in each of the 3 groups.
Teratology Study
Maass et al administered triamterene in doses ranging from 11.1 to 32.0 mg/kg/day to 4 groups of 15 female rats on the 8th through 10th day of gestation to investigate its effect on maternal weight gain, litter size and live birth index. Adverse effects on fetal tissue could not be demonstrated nor were physical abnormalities observed in the progeny.