


Product Monograph - Mylan-Amilazide
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| oral | Tablet 5mg of Amiloride Hydrochloride and 50 mg of Hydrochlorothiazide | None For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Mylan-Amilazide (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) is indicated for:
- the maintenance therapy of patients with hepatic cirrhosis with ascites and edema.
- the maintenance therapy of those patients with edema of cardiac origin or with arterial hypertension who are hypokalemic or in whom maintenance of normal potassium levels is considered to be clinically important i.e., digitalized patients, patients in whom adequate dietary intake of potassium is not feasible or patients with cardiac arrhythmias.
Fixed-dose combination drugs are not indicated for initial therapy. Patients should be titrated on the individual drugs. If the fixed combination represents the dosage so determined, its use may be more convenient in patient management. If during maintenance therapy dosage adjustment is necessary it is advisable to use the individual drugs.
Use in Hepatic Cirrhosis with Ascites and Edema
Amiloride hydrochloride used alone may provide satisfactory diuresis with diminished potassium loss and with a reduced risk of metabolic alkalosis. In resistant cases amiloride hydrochloride may be used with kaliuretic-diuretic agents to help produce satisfactory diuresis, while maintaining a more balanced serum electrolyte pattern. As
with all therapy for the ascites of hepatic cirrhosis, gradual weight loss and avoidance of electrolyte imbalance are the chief objectives (see PRECAUTIONS).
Pediatrics:
The safety and effectiveness of Mylan-Amilazide (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) in children have not been established.
CONTRAINDICATIONS
Hyperkalemia
MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) should not be used in the presence of elevated serum potassium levels (see WARNINGS).
Antikaliuretic Therapy or Potassium Salts
Other antikaliuretic agents and potassium supplements are contraindicated in patients receiving MYLAN-AMILAZIDE (such combination therapy is commonly associated with rapid increases in plasma potassium levels).
Impaired Renal Function
Anuria, acute renal failure, severe or progressive renal disease, and diabetic nephropathy are contraindications to the use of MYLAN-AMILAZIDE (see WARNINGS)
Hypersensitivity
MYLAN-AMILAZIDE is contraindicated in patients who are hypersensitive to any component of this medication, or to other sulfonamide-derived drugs.
WARNINGS AND PRECAUTIONS
Hyperkalemia
Hyperkalemia, i.e., serum potassium levels over 5.5 mEq per litre, has been observed in some patients who received amiloride hydrochloride either alone or with diuretics. This has been noted particularly in elderly patients, in diabetic patients, and in hospitalized patients with hepatic cirrhosis or cardiac edema who had known renal impairment, were seriously ill, or were receiving vigorous diuretic therapy. Since fatalities have occurred in such patients, they should be monitored carefully for clinical, laboratory, and electrocardiographic (ECG) evidence of hyperkalemia and for acidosis. Monitoring of
the serum potassium level is important because hyperkalemia is not always associated with an abnormal ECG.
Warning signs or symptoms of hyperkalemia include paresthesias, muscular weakness, fatigue, flaccid paralysis of the extremities, bradycardia, shock, and ECG abnormalities.
When abnormal, the ECG in hyperkalemia is characterized primarily by tall, peaked T waves or elevations from previous tracings. There may also be lowering of the R wave and increased depth of the S wave, widening and even disappearance of the P wave, progressive widening of the QRS complex, prolongation of the PR interval, and ST depression.
Potassium supplementation in the form of medication or a potassium-rich diet should not be used with MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) except in severe and/or refractory cases of hypokalemia. If potassium supplementation is used, careful monitoring of the serum potassium level is recommended.
Treatment of Hyperkalemia
If hyperkalemia occurs in patients taking MYLAN-AMILAZIDE the drug should be discontinued immediately. If the serum potassium level exceeds 6.5 mEq per litre, active measures should be taken to reduce it. Such measures include the intravenous administration of sodium bicarbonate solution or oral or parenteral glucose with a rapid-acting insulin preparation. If needed, a cation exchange resin such as sodium polystyrene sulfonate may be given orally or by enema. Patients with persistent hyperkalemia may require dialysis.
Endocrine & Metabolism
Diabetes Mellitus
In diabetic patients, hyperkalemia has been commonly reported with the use of amiloride hydrochloride, particularly if they have chronic renal disease or prerenal azotemia. Some deaths occurred in this last group of patients. Therefore, if therapy with amiloride hydrochloride is considered essential, the drug should be used with caution in diabetic or suspected diabetic patients and only after first determining the status of renal function.
Careful monitoring of serum potassium levels is required throughout the therapy.
One patient with poorly controlled diabetes mellitus who became severely hyperkalemic while on amiloride hydrochloride died following two repeated intravenous glucose tolerance tests. Therefore, amiloride hydrochloride should be
discontinued at least 3 days before glucose tolerance testing.
__________________________________________________________________
In diabetic patients, insulin requirements may be increased, decreased, or unchanged due to the hydrochlorothiazide component. Diabetes mellitus which has been latent may become manifest during administration of thiazide diuretics.
Metabolic or Respiratory Acidosis
Antikaliuretic therapy should be instituted only with caution in patients in whom respiratory or metabolic acidosis may occur, such as patients with cardiopulmonary disease or diabetes. If MYLAN-AMILAZIDE is given to the patients, frequent monitoring of acid-base balance is necessary. Shifts in acid-base balance alter the ratio of extracellular/intracellular potassium, and the development of acidosis may be associated with rapid increases in serum potassium levels.
Metabolism
Hyperuricemia may occur or gout may be precipitated in certain patients receiving thiazide therapy.
Thiazides may decrease serum PBI levels without signs of thyroid disturbance.
Magnesium excretion is increased. This may result in hypomagnesemia.
Thiazides may decrease urinary calcium excretion. Thiazides may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may be evidence of hidden hyperparathyroidism. Thiazides should be discontinued before carrying out tests for parathyroid function.
Increases in cholesterol and triglyceride levels may be associated with thiazide diuretic therapy.
Other
Patients should be observed regularly for the possible occurrence of liver dysfunction, idiosyncratic reactions, or blood dyscrasias.
Renal
Impaired Renal Function and/or Azotemia
When creatinine clearance falls below 30 mL/min thiazide diuretics are ineffective.
In patients with impaired renal function azotemia may be precipitated or increased by hydrochlorothiazide. Cumulative effects of the drug may develop in patients with impaired renal function. Careful monitoring of such patients is therefore necessary. If increasing azotemia and oliguria occur during treatment MYLAN-AMILAZIDE should be discontinued.
Patients with impaired renal function other than those listed under
CONTRAINDICATIONS and who have BUN levels over 30 mg per 100 mL, serum creatinine levels over 1.5 mg per 100 mL, or blood urea values over 60 mg per 100 mL should not receive the drug without careful, frequent monitoring of serum electrolytes, creatinine, and BUN levels. Potassium retention associated with the use of MYLAN-AMILAZIDE is accentuated in the presence of renal impairment and may result in the rapid development of hyperkalemia. Prolongation of amiloride hydrochloride excretion was observed in patients with renal impairment.
Hepatic
Hepatic Disease
Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma.
Immune
Hypersensitivity Reactions
Sensitivity reactions to thiazides may occur in patients with or without a history of allergy or bronchial asthma.
The possibility of exacerbation or activation of systemic lupus erythematosus has been reported with the thiazides.
Electrolyte Imbalance and BUN Increases
Although the likelihood of electrolyte imbalance is lessened with MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets), careful check should be kept for signs of fluid and electrolyte imbalance: namely, hyponatremia, hypochloremic alkalosis, hypokalemia and hypomagnesemia. It is particularly important to make serum and urine electrolyte determinations when the patient is vomiting excessively or receiving parenteral fluids. Warning signs or symptoms of fluid and electrolyte imbalance include: dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, seizures, confusion, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting.
Hypokalemia may develop with hydrochlorothiazide as with any other potent diuretic, especially with brisk diuresis, after prolonged therapy or when severe cirrhosis is present. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g., increased ventricular irritability).
__________________________________________________________________
Diuretic induced hyponatremia is usually mild and asymptomatic. In a few patients hyponatremia may become severe and symptomatic. Such patients require immediate attention and appropriate treatment.
Hypochloremia may occur during the use of MYLAN-AMILAZIDE. Any chloride deficit is usually mild and may be corrected by the use of ammonium chloride (except in patients with hepatic disease) and largely prevented by a near normal salt intake.
Increases in BUN levels have been reported and have usually accompanied vigorous fluid elimination, especially when diuretic combinations were used in seriously ill patients, such as those who have hepatic cirrhosis with ascites and metabolic alkalosis, or those with resistant edema. Therefore, careful monitoring of serum electrolytes and BUN levels is important when using MYLAN-AMILAZIDE.
Effects Related to Diuresis in Cirrhotic Patients
Patients with hepatic cirrhosis and ascites are intolerant of acute shifts in electrolyte balance and often have pre-existing hypokalemia as a result of associated secondary hyperaldosteronism. When oral diuretic therapy is used, these patients should be carefully monitored and diuresis should be gradual.
Hepatic encephalopathy, manifested by tremors, confusion, and coma, has been reported in association with amiloride hydrochloride therapy.
In cirrhotic patients receiving amiloride hydrochloride alone, jaundice associated with the underlying disease process has deepened in a few instances, but the relationship to the drug is uncertain.
Special Populations
Pregnant Women
Because clinical experience is limited, MYLAN-AMILAZIDE is not recommended for use during pregnancy.
The routine use of diuretics in otherwise healthy pregnant women with or without mild edema is not recommended and exposes mother and fetus to unnecessary hazard. Diuretics do not prevent development of toxemia of pregnancy and there is no satisfactory evidence that they are useful in the treatment of toxemia.
Teratologic studies with amiloride hydrochloride in rabbits and mice revealed no evidence of harm to the fetus. Reproduction studies in rats showed no evidence of impaired fertility. At approximately 5 or more times the expected maximum daily dose for humans, some toxicity was seen in adult rats and rabbits and a decrease in rat pup growth and survival occurred.
In rats a trace of drug crossed the placental barrier.
Thiazides cross the placental barrier and appear in the cord blood. Therefore, the use of MYLAN-AMILAZIDE when pregnancy is present or suspected requires that the benefits of the drug be weighed against possible hazards to the fetus. These hazards include fetal or neonatal jaundice, thrombocytopenia and possibly other side effects that have occurred in the adult.
Nursing Women
It is not known whether amiloride hydrochloride is excreted in human milk. In rats secretion of amiloride hydrochloride in milk has been demonstrated. Thiazides appear in breast milk. Because of the potential for serious adverse reactions in nursing infants, if the use of MYLAN-AMILAZIDE is deemed essential, the patient should stop nursing.
Pediatrics
The safety for use of amiloride hydrochloride in children has not been established; therefore, MYLAN-AMILAZIDE is not recommended in the pediatric age group.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
While rare, the most serious adverse effect of Amiloride Hydrochloride and Hydrochlorothiazide is symptomatic hyperkalemia. Other metabolic changes that occur are asymptomatic hyperkalemia, hypokalemia, and hypochloremia.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse drug reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The following incidence of other adverse reactions was determined from clinical trials (607 patients treated with Amiloride Hydrochloride and Hydrochlorothiazide) [see table below].
__________________________________________________________________
Incidence ≥ 3% Incidence >1% - <3% Incidence ≤ 1%
Gastrointestinal
(In 7.1% of patients) Nausea/anorexia (3.7%) Diarrhea Constipation Gastrointestinal pain GI bleeding Abdominal pain GI disturbance Appetite changes Abdominafullness Hiccups Thirst Vomiting Flatulence Bad taste
Central Nervous System
(In 13.9% of patients) Headache (7.8%) Paresthesia/ numbness Dizziness (6.1%) Stupor Weakness (4.0%) Vertigo Insomnia Nervousness Depression Sleepiness Mental confusion Visual disturbance
Dermatologic
(in 5.2% of patients) Rash (3.4%) Pruritus Flushing
Cardiovascular
(In 4.3% of patients) Arrhythmia Tachycardia Digitalis toxicity
Orthostatic hypotension Angina pectoris
Musculoskeletal
(in 3.7% of patients) Leg ache Muscle cramps/spasm Joint pain Chest pain Back pain
Respiratory
(in 2.6% of patients) Dyspnea Nasal congestion
Incidence ≥ 3% Incidence >1% - <3% Incidence ≤ 1%
Urogenital
(In 1.7% of patients)
Impotence Nocturia Dysuria Incontinence
Endocrine
(in 0.9% of patients) Gout Dehydration
Other
(in 2.6% of patients) Fatigue/tiredness Malaise
Other adverse reactions reported with Amiloride Hydrochloride and Hydrochlorothiazide are listed below:
Body as a Whole
Syncope
Metabolic
Elevated serum potassium levels (>5.5 mEq per liter)
Electrolyte imbalance
Hyponatremia (See PRECAUTIONS)
Symptomatic hyponatremia
Integumentary
Diaphoresis
Urogenital
Renal dysfunction including renal failure
Other adverse reactions that have been reported with the individual components are listed below:
Amiloride
Body as a Whole
Neck/shoulder ache
Pain in extremities
Digestive
Abnormal liver function
Activation of pre-existing peptic ulcer
__________________________________________________________________
Dyspepsia
Jaundice
Integumentary
Dry mouth
Alopecia
Nervous
Tremors
Encephalopathy
Hematologic
Neutropenia
Aplastic anemia
Cardiovascular
One patient with a partial heart block developed complete heartblock Palpitation
Psychiatric
Decreased libido
Somnolence
Respiratory
Cough
Special Senses
Tinnitus
Increased intraocular pressure
Urogenital
Polyuria
Urinary frequency Bladder spasm
Hydrochlorothiazide
Body as a Whole Anaphylactic reactions Fever
Cardiovascular
Necrotizing angiitis (vasculitis, cutaneous vasculitis)
Digestive
Jaundice (intrahepatic cholestatic jaundice) Pancreatitis
Cramping
Gastric irritation
Endocrine/Metabolic Glycosuria
Hyperglycemia
Hyperuricemia
Hypokalemia
Hematologic
Agranulocytosis
Aplastic anemia
Hemolytic anemia
Leukopenia
Purpura
Thrombocytopenia
Integumentary
Photosensitivity
Sialadenitis
Urticaria
Toxic-epidermal necrolysis
Psychiatric
Restlessness
Renal
Interstitial nephritis
Respiratory
Respiratory distress including pneumonitis and pulmonary edema
Special Senses
Transient blurred vision Xanthopsia
DRUG INTERACTIONS
Drug-Drug Interactions
Lithium
__________________________________________________________________
Lithium should generally not be given to patients receiving diuretics. Diuretic agents reduce the renal clearance of lithium and add a high risk of lithium toxicity; concomitant use is not recommended. Refer to the Product Monograph for lithium preparations before use of such preparations.
Non-Steroidal Anti-inflammatory Drugs
In some patients, the administration of a non-steroidal anti-inflammatory agent can reduce the diuretic, natriuretic and hypertensive effects of diuretics. Concomitant administration of non-steroidal anti-inflammatory drugs (NSAIDs) and potassium-sparing agents, including amiloride HCl, may cause hyperkalemia and renal failure, particularly in elderly patients. Therefore, when amiloride HCl is used concomitantly with NSAIDs, renal function and serum potassium levels should be carefully monitored.
Others
When amiloride hydrochloride is administered concomitantly with an angiotensin-converting enzyme inhibitor, cyclosporine or tacrolimus, the risk of hyperkalemia may be increased. Therefore, if concomitant use of these agents is indicated because of demonstrated hypokalemia, they should be used with caution and with frequent monitoring of serum potassium.
When given concurrently the following drugs may interact with thiazide diuretics.
Other Antihypertensive Drugs
Hydrochlorothiazide potentiates the action of other antihypertensive drugs. Therefore, the dosage of these agents, especially the ganglion blockers, may need to be reduced when MYLAN-AMILAZIDE is added to the regimen.
Skeletal Muscle Relaxants, Nondepolarizing
Thiazide-containing drugs may increase the responsiveness to tubocurarine.
Pressor Amines
Hydrochlorothiazide may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude the effectiveness of the pressor agent for therapeutic use.
Alcohol, Barbiturates, or Narcotics
In the presence of thiazide diuretics, potentiation of orthostatic hypotension may occur.
Antidiabetic Drugs (Oral Agents and Insulin)
Dosage adjustment of the antidiabetic drug may be required. Insulin requirements in diabetic patients treated with thiazide diuretics may be increased. Diabetes mellitus which has been latent may become manifest during thiazide administration.
Cholestyramine and Colestipol Resins
Absorption of hydrochlorothiazide is impaired in the presence of anionic exchange resins. Single doses of either cholestyramine or colestipol resins bind the hydrochlorothiazide and reduce its absorption from the gastrointestinal tract by up to 85 and 43% respectively.
Corticosteroids, ACTH
Intensified electrolyte depletion, particularly hypokalemia may occur when given concomitantly with thiazide diuretics.
Drug-Laboratory Interactions
Because of their effects on calcium metabolism, thiazides may interfere with tests for parathyroid function (see WARNINGS AND PRECAUTIONS).
DOSAGE AND ADMINISTRATION
Dosing Considerations
(See WARNINGS AND PRECAUTIONS)_
Recommended Dose and Dosage Adjustment
Optimal dosage should be established by the individual titration of the components.
Maintenance doses may be lower than those required to initiate diuresis; therefore, reduction in the daily dosage should be attempted when the patient's weight is stabilized. In cirrhotic patients, gradual weight reduction is especially desirable to reduce the likelihood of untoward reactions associated with diuretic therapy.
Hepatic Cirrhosis with Ascites and Edema
The usual maintenance dose of MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) is 1 tablet given once a day. The dosage should not exceed 4 tablets a day in single or divided doses.
__________________________________________________________________
Edema of Cardiac Origin
The usual maintenance dose of MYLAN-AMILAZIDE is 1 or 2 tablets given once a day or in divided doses. The dosage should not exceed 4 tablets a day. Therapy may be on an intermittent basis.
Hypertension
The usual maintenance dosage is 1 or 2 tablets given once a day or in divided doses. The dosage should not exceed 4 tablets a day.
OVERDOSAGE
No data are available in regard to overdosage in humans with MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) or with the amiloride hydrochloride component.
The most common signs and symptoms to be expected from overdosage with MYLAN-AMILAZIDE are dehydration and electrolyte imbalance. Serum electrolytes should be carefully monitored with special attention to potassium levels. If hyperkalemia occurs, active measures should be taken to reduce the serum potassium levels.
Cardiac arrhythmias may be caused by abnormal potassium levels. Digitalized patients are especially prone to arrhythmias.
No specific information is available on the treatment of overdosage with MYLAN-AMILAZIDE and no specific antidote is available. Treatment is symptomatic and supportive. Therapy with MYLAN-AMILAZIDE should be discontinued and the patient observed closely. Suggested measures include induction of emesis and/or gastric lavage.
It is not known whether the drug is dialyzable.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
MYLAN-AMILAZIDE (Amiloride Hydrochloride and Hydrochlorothiazide Tablets) is a diuretic/antihypertensive combining the potent natriuretic action of hydrochlorothiazide with the potassium-conserving property of amiloride hydrochloride. The mild diuretic and antihypertensive actions of amiloride hydrochloride are additive to the natriuretic, diuretic and antihypertensive activity of the thiazide while minimizing the loss of potassium and bicarbonate and lessening the likelihood of acid-base imbalance. The onset of the diuretic action of MYLAN-AMILAZIDE is within 1 to 2 hours and this action appears to be sustained for approximately 24 hours.
Pharmacodynamics
Hydrochlorothiazide
Hydrochlorothiazide is a diuretic and antihypertensive agent. It affects the renal tubular mechanism of electrolyte reabsorption.
Hydrochlorothiazide increases excretion of sodium and chloride in approximately equivalent amounts. Natriuresis may be accompanied by some loss of potassium and bicarbonate. While this compound is predominantly a saluretic agent, in vitro studies have shown that it has a carbonic anhydrase inhibitory action which seems to be relatively specific for the renal tubular mechanism. It does not appear to be concentrated in erythrocytes or the brain in sufficient amounts to influence the activity of carbonic anhydrase in those tissues.
Hydrochlorothiazide is useful in the treatment of hypertension. It may be used alone or as an adjunct to other antihypertensive drugs.
Hydrochlorothiazide does not decrease normal blood pressure.
The onset of the diuretic action of hydrochlorothiazide occurs in 2 hours and the peak action in about 4 hours. Diuretic activity lasts about 6 to 12 hours.
Amiloride Hydrochloride
Amiloride hydrochloride is an antikaliuretic drug with mild natriuretic diuretic and antihypertensive activity. These activities may be additive to the effects of thiazides or other saluretic-diuretic agents. The principal use of amiloride hydrochloride is to conserve potassium in selected patients receiving kaliuretic-diuretic agents. The action is not related to the level of aldosterone excretion. Amiloride hydrochloride is not an aldosterone antagonist. The drug acts directly on the distal portion of the
__________________________________________________________________
nephron. Amiloride hydrochloride causes an increase in sodium excretion and a decrease in potassium and hydrogen ion excretion. Chloride excretion may remain unchanged or increase slowly with continued therapy.
Pharmacokinetics
Hydrochlorothiazide
Hydrochlorothiazide is not metabolized but is eliminated rapidly by the kidney. The plasma half-life is 5.6-14.8 hours when the plasma levels can be followed for at least 24 hours. At least 61% of the oral dose is eliminated unchanged within 24 hours. Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk.
Amiloride Hydrochloride
Approximately 50% of an oral dose is absorbed. Amiloride hydrochloride usually begins to act within 2 hours after an oral dose. Its effect on electrolyte excretion reaches a peak between 6 and 10 hours and lasts about 24 hours. Peak plasma levels are obtained in 3 to 4 hours and plasma half-life varies from 6 to 9 hours.
Amiloride hydrochloride is not metabolized by the liver. About 50% of a 20 mg dose of amiloride hydrochloride is excreted unchanged in the urine and 40% is excreted in the stool within 72 hours. In clinical studies amiloride hydrochloride was found to have little effect on glomerular filtration rate or renal blood flow.
STORAGE AND STABILITY
Temperature:
Store between 15 ºC and 30 ºC in a tightly closed container.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Composition:
Each tablet contains 5 mg amiloride hydrochloride, 50 mg hydrochlorothiazide, and the following non-medicinal ingredients: lactose, dibasic calcium phosphate, guar gum, starch, magnesium stearate and sunset yellow FCF.
Dosage forms and availability:
MYLAN-AMILAZIDE (amiloride hydrochloride and hydrochlorohtiazide) tablets are peach-colored, diamond-shaped, compressed tablets, with a functional scoreline on one side and “5/50” on the other side. Available in bottles of 100s and 1000’s 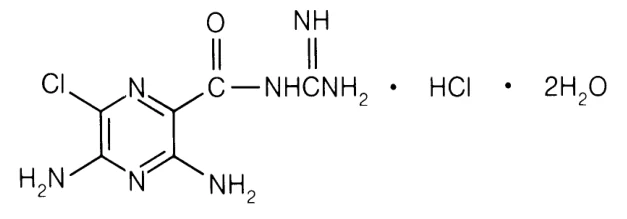
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Amiloride Hydrochloride
Chemical name: 3,5-diamino-N-(aminoiminomethyl)-6-
chloropyrazinecarboxamide monohydrochloride dihydrate.
Molecular formula : C6H8CIN7O•HCl•2H2O
Molecular mass: 302.12
Structural formula:
Physicochemical properties:
Amiloride hydrochloride is a yellow to greenish yellow, odourless or practically odorless, crystalline compound, soluble in water. It is the salt of a moderately strong base, amiloride, pKa 8.7.
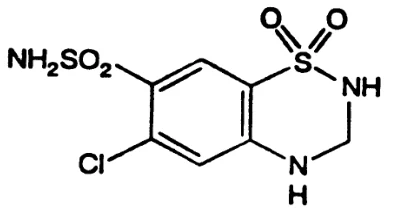
Proper name: Hydrochlorothiazide
Chemical name: 6-chloro-3,4-dihydro-2H-1,2,4-benzothiadiazine-7- sulfonamide1,1-dioxide.
Molecular formula: C7H8CIN3O4S2 Molecular mass: 297.74
__________________________________________________________________
Structural formula:
Physicochemical properties:
Hydrochlorothiazide is a white or practically white crystalline compound with low solubility in water, but is readily soluble in dilute aqueous sodium hydroxide.
DETAILED PHARMACOLOGY
Hydrochlorothiazide
Hydrochlorothiazide has diuretic and antihypertensive activities. This compound increases the excretion of sodium and chloride in approximately equivalent amounts and causes a simultaneous, usually minimal loss of bicarbonate. The excretion of ammonia is reduced slightly by hydrochlorothiazide and the blood ammonia concentration may be increased. The excretion of potassium is increased slightly. Calcium excretion is decreased by hydrochlorothiazide and magnesium excretion is increased.
Hydrochlorothiazide is eliminated rapidly by the kidney. Its rate of elimination is decreased somewhat by the coadministration of probenecid without, however, an accompanying reduction in diuresis.
Amiloride Hydrochloride
Amiloride hydrochloride is chemically unrelated to other known antikaliuretic or diuretic agents. It is a salt of a moderately strong base (pKa 8.7).
In rats and dogs, amiloride hydrochloride in an oral dose of 0.1 mg/kg or less increases the excretion of sodium and, to a lesser extent, of chloride but does not increase the excretion of potassium.
A potassium-retaining effect is seen in experimental animals, especially under conditions of high potassium excretion, as upon loading with potassium chloride, after pretreatment with acetazolamide or thiazides, or in deoxycorticosterone-treated
adrenalectomized rats. The natriuresis is accompanied by an increase in urinary pH, reflecting a decrease in hydrogen ion excretion.
Following oral administration to dogs, amiloride hydrochloride increases the rate of sodium excretion less than do the more potent agents, but the moderate effect on sodium excretion has an extended duration. Natriuresis increases only moderately as the oral dose is increased from 0.25 to 4.0 mg/kg, this activity persists beyond 6 hours.
An increase in sodium excretion is produced when amiloride hydrochloride is given together with chlorothiazide, hydrochlorothiazide, or acetazolamide to rats. Amiloride hydrochloride antagonizes the kaliuretic effect of the other diuretic. Oral doses of amiloride hydrochloride (0.1 to 0.5 mg/kg) increase the excretion of sodium and decrease that of potassium in dogs given ethacrynic acid (1.0 mg/kg) or hydrochlorothiazide (0.5 mg/kg) orally.
Amiloride hydrochloride increases the Na+/K+ excretion ratio in adrenalectomized rats. In adrenalectomized rats treated with aldosterone, deoxycorticosterone, or hydrocortisone, amiloride hydrochloride not only reverses the steroid-induced sodium retention, but increases the Na+/K+ excretion ratio substantially above that of untreated adrenalectomized rats.
Stop-flow studies in dogs indicate that amiloride hydrochloride inhibits tubular secretion of potassium and reabsorption of sodium in the distal portion of the nephron. In renal clearance studies, 1.0 mg/kg intravenously did not affect glomerular filtration rate, effective renal plasma flow, or glucose reabsorption. An enzymatic basis for the renal action of amiloride hydrochloride has not been elucidated. It is not an inhibitor of carbonic anhydrase.
Amiloride hydrochloride given parenterally (2.5 to 5.0 mg/kg) to anesthetized dogs produces profound reduction of blood pressure and produces changes in the electrocardiogram. The effects which are coincident with the release of histamine into plasma, are not seen if the compound is injected slowly or if lower doses are given. A slight increase in gastric secretion and intestinal motility occurred after oral administration to dogs of 0.5 to 2.0 mg/kg. Pretreatment of several days with amiloride hydrochloride in a dose of 5 mg/kg/day by mouth does not alter the response of dogs to ouabain.
TOXICOLOGY
Acute Toxicity
__________________________________________________________________
| ORAL LD50 (mg/kg) | |||
| SPECIES | Amiloride Hydrochloride | Hydrochlorothiazide | Amiloride Hydrochloride/ Hydrochlorothiazide 5:50 |
| MICE | 56 | >10,000 | 189 |
| RATS | 36 - 85 | >10,000 | 422 (females) 377 (males) |
Acute oral studies of fixed combinations in the mouse and rat showed that the toxicity was based primarily on the amiloride content.
Subacute and Chronic Toxicity
Amiloride Hydrochloride/Hydrochlorothiazide
Twelve-week and 25-week oral studies of the combination in the rat indicated the toxicity expected from the individual ingredients (fluid loss at high doses and hyperplasia of the adrenal zona glomerulosa). No evidence of drug interaction was seen. The high dose in the 12-week study (10 mg/kg of amiloride hydrochloride with 500 mg/kg of hydrochlorothiazide) was not well tolerated; 7 of 15 males and 4 of 15 females died.
The toxicity was related to effects on serum electrolytes.
In the dog, effects observed included dry nose and gums, diuresis, natriuresis, chloruresis, antikaluresis, and hyperplasia of the adrenal zona glomerulosa. Electrocardiographic changes suggestive of potassium retention were seen at high dose levels. A dose of 5/50 mg/kg resulted in deaths from electrolyte imbalance. A dose of 2.5/25 mg/kg increased to 4/40 mg/kg/day was tolerated for six months.
Amiloride Hydrochloride
MODERATE TO MARKED HYPERKALEMIA DEVELOPED AT DOSES GREATER THAN 8.0 mg/kg/day. ELECTROCARDIOGRAPHIC CHANGES WERE OBSERVED. SERUM SODIUM AND CHLORIDE DECREASED.
Rats were administered 0, 2.5, 5, 10 or 20 mg/kg/day of amiloride for 5 weeks by the oral route. The lower doses showed mild toxicity; gastric lesions, similar to stress ulcers, were observed at 10 and 20 mg/kg/day.
Superficial ulceration of the stomach or intestine was seen in 2 of 12 dogs in a 6 week oral study.
Rats received amiloride hydrochloride by oral route at doses of 0, 2.5, 5.0 and 10 to 15 mg/kg for up to 80 weeks. Inhibition of weight gain occurred in male rats. Treatment related changes included alterations in urinary and serum sodium and potassium, renal tubular dilatation and a dose-dependent hyperplasia of the adrenal zona glomerulosa. Hypotonia of muscles, loss of righting reflex and coma occurred in moribund rats (high dose group). Symptoms of electrolyte imbalance including paraphimosis, occurred at doses of 10 mg/kg/day during a one year study.
Dogs treated with oral doses of 0, 2, 4 and 8 mg/kg/day (base) for one year showed changes in body weight, water intake and serum electrolytes. Positive fecal occult blood occurred at a slightly greater incidence in treated animals but no evidence of gastrointestinal ulceration was seen. Doses producing marked electrolyte changes had no effect on blood glucose or glucose tolerance. Dose-dependent hyperplasia of the zona glomerulosa of the adrenal was observed in all treated dogs.
In monkeys treated with oral doses of 0, 2, 4 and 8 (increased to 15.8) mg/kg/day for one year, excitable and irritable behavior occurred at the highest dose. Increase in serum potassium and decrease in serum sodium occurred at doses as low as 4 mg/kg/day. Although adrenal glands of some high and middle dose animals appeared enlarged, hyperplasia of the zona glomerulosa was not observed. Urinary excretion of aldosterone was increased in high dose animals.
Special Studies Relative to Adrenal Zona Glomerulosa, Hyperplasia and Diabetes
Amiloride hydrochloride produced a dose-dependent hyperplasia of the zona glomerulosa of the adrenal cortex in rats and dogs and to a lesser extent in monkeys. In rats, reversibility of the hyperplasia was demonstrated after the drug was given for 58 weeks and the animals were observed for an additional 22 weeks. Hyperplasia has been shown to disappear in 19 to 30 days after cessation of treatment and the adrenals were normal within 30 to 58 days. The hyperplasia can be reduced by substitution of physiologic saline for drinking water. Hyperplasia of the adrenal zona glomerulosa occurred in maternal mice but not in the offspring in a teratogenic study. The hyperplasia is considered to be induced by alteration of serum electrolytes and/or inhibition of aldosterone activity.
No effect on carbohydrate metabolism was observed when the toxicity of amiloride hydrochloride was studied in obese diabetic Zucker rats and normal-thin rats. Amiloride hydrochloride had no adverse effect on glucose tolerance in acute experiments in rats or in a chronic study in dogs.
The effect of amiloride hydrochloride on I131 uptake was measured in immature female rats. A dose of about 5 or 10 mg/kg/day given subcutaneously every 8 hours for 21 days did not alter I131 uptake.
Hydrochlorothiazide
In dogs given doses of 250, 500 and 1000 mg/kg seven days a week for 8 weeks, no gross signs of drug effect were noted except for electrolyte imbalance.
Chronic oral toxicity studies in the rat using doses of up to 2000 mg/kg/day 5 days per week for 26 weeks showed no signs of drug effect and no drug-related changes on post mortem examination. In dogs, oral doses of 0, 125, 250 mg/kg/day 5 days per week for 26 weeks; 500 mg/kg/day for 7 weeks; 11 weeks without drug then 500 mg/kg/day for 7 days per week for 8 weeks were given. Slight depression of plasma potassium, small amounts of yellow crystalline precipitate in the bladder in two of twelve dogs were found on gross examination. Histomorphologic studies did not show drug-related changes.
Tumorigenicity Studies
No tumorigenic effect was observed when amiloride hydrochloride was administered for 92 weeks to mice at doses of up to 10 mg/kg/day and for 104 weeks to rats at doses of up to 8 mg/kg/day.
Reproductive Studies
Amiloride hydrochloride/hydrochlorothiazide combinations were administered orally to pregnant mice at dosage levels of 1/5, 5/25, and 5/50 mg/kg/day (12.5 times the expected maximum daily dose for humans) and to pregnant rabbits at dosage levels of 1.0/2.5, 1/5, and 4/20 mg/kg/day (10/20 times the expected maximum daily dose for humans). In a second study in pregnant rabbits, amiloride hydrochloride/hydrochlorothiazide was administered at dosage levels of 0.5/5, 1/10, and 2/20 mg/kg/day (5 times the expected maximum daily dose for humans). No teratogenic, embryotoxic, fetotoxic, or maternotoxic effects attributable to treatment were observed in either species.
No effect on reproductive performance or fertility in albino rats (COBS strain) given 2, 4, or 8 mg/kg/day amiloride base orally was noted. Growth rate and food consumption were reduced at the highest dose. Doses of 4 and 8 mg/kg/day were administered without effect during late gestation and growth. The high dose adversely affected pup survival and growth.
____________________________________________________________________________________ REFERENCES
- 1. Antcliff AC, Beevers DG, Hamilton M, Harpur JE. The use of amiloride hydrochloride in the correction of hypokalaemic alkalosis induced by diuretics. Postgrad Med J 1971;47:644-7.
- 2. Bergstrom J, Fridén AM. The effect of hydrochlorothiazide and amiloride administered together on muscle electrolytes in normal subjects. Acta Med Scand 1975;197:415-9.
- 3. Borhani NO. Chlorothiazide and hydrochlorothiazide: A comparative study of their hypotensive saluretic and hyperuricemic action. Ann Int Med 1960;53(2):342-58.
- 4.
Bull MB, Laragh JH. Amiloride, a potassium-sparing natriuretic agent. Circulation
1968;37:45-53.
- 5.
Bryant JM, et al. The hypotensive effects of chlorothiazide and hydrochlorothiazide:
A critical comparison. Am J Cardiol 1961;7(3):392-5.
- 6. Castenfors H. Long-term treatment with a fixed combination of amiloride hydrochloride and hydrochlorothiazide, Recent studies: Diuresis, kaliuresis, and hypertension: Long-term clinical experience with a fixed combination of amiloride hydrochloride and hydrochlorothiazide. Proceedings of an international workshop held in Bologna, Italy, Dec 14, 1976; Bruno Magnani (ed.), Futura Publishing Co., Inc., Mt Kisco, N.Y. 1977;27-35.
- 7. Eisalo A, Kohvakka A. Serum potassium levels with a fixed combination of amiloride hydrochloride and hydrochlorothiazide, Recent studies: Diuresis, kaliuresis, and hypertension: Long-term clinical experience with a fixed combination of amiloride hydrochloride and hydrochlorothiazide. Proceedings of an international workshop held in Bologna, Italy, Dec 14, 1976; Bruno Magnani (ed), Futura Publishing Co., Inc., Mt Kisco, N.Y. 1977;1-11.
- 8. Gombos EA, Freis ED, Moghadam A. Effect of MK-870 in normal subjects and hypertensive patients. N Engl J Med 1966;275:1215-20.
- 9. Grenfell RF, Briggs AH, Holland WC. Hypotensive effects of some antihypertensive drugs. Clin Pharmacol Ther 1963;4(2):162-71.
- 10.
Hamdy RC, Tovey J, Perera N. Hypokalaemia and diuretics. Br Med J
1980;280:1187.
- 11. Lammintausta R, Kanto J, Mäntylä R. Renin-aldosterone system and urinary electrolytes after amiloride, hydrochlorothiazide and the combination. Int J Clin Pharmacol Biopharm 1978;16(11):503-7.
- 12. MacFarlane JPR. Long-term use of a fixed combination of amiloride hydrochloride and hydrochlorothiazide in elderly patients, Recent studies: Diuresis, kaliuresis, and hypertension: Long-term clinical experience with a fixed combination of amiloride hydrochloride and hydrochlorothiazide. Proceedings of an international workshop held in Bologna, Italy, Dec 14, 1976; Bruno Magnani (ed), Futura Publishing Co., Inc., Mt Kisco, N.Y. 1977;82-9.
- 13. Moduret® Product Monograph Prempharm Inc. April 8 2005.
- 14. Paterson JW, Dollery CT, Haslam RM. Amiloride hydrochloride in hypertensive patients. Br Med J 1968;1:422-3.
- 15. Pearce VR, Antcliff AC, Beevers DG, Hamilton M. Total exchangeable potassium in response to amiloride. Postgrad Med J 1978;54(634):533-7.
- 16.
Sherlock S. Diseases of the liver and biliary system (5th Edition), Blackwell Scientific
Publications, 1975.
- 17. Smirk H, McQueen EG, Morrison RBI. Chlorothiazide and hydrochlorothiazide in management of hypertension. Br Med J 1960;1:515-8.
- 18.
Van Soeren F. The antihypertensive and biochemical effects of
hydrochlorothiazide/amiloride (MODURETIC®) versus chlorthalidone. J Int Med Res 1980;8:132-5.
- 19. Waal-Manning HJ, Simpson FO. A fixed combination of amiloride hydrochloride and hydrochlorothiazide in the treatment of hypertension, Recent studies: Diuresis, kaliuresis, and hypertension: Long-term clinical experience with a fixed combination of amiloride hydrochloride and hydrochlorothiazide. Proceedings of an international workshop held in Bologna, Italy, Dec 14, 1976; Bruno Magnani (ed), Futura Publishing Co., Inc., Mt Kisco, N.Y. 1977;48-63.
- 20.
Wan HH, Lye MDW. Moduretic-induced metabolic acidosis and hyperkalaemia.
Postgrad Med J 1980;56:348-50.
- 21. Whight C, Morgan T, Carney S, Wilson M. Diuretics, cardiac failure and potassium depletion: A rational approach. Med J Aust 1974;2:831-3.
- 22.
Wolf RL, Mendlowitz M, Roboz J, Gitlow SE. Treatment of hypertension with antihypertensive diuretic drugs. Am Heart J 1966;72:692-7.
____________________________________________________________________________________
- 23.
Yamada S, Reynolds TB. Amiloride (MK-870), A new antikaluretic diuretic:
Comparison to other antikaluretic diuretics in patients with liver disease and ascites. Gastroenterology 1970;59:833-41.
- 24. Zsotér TT, Hart F, Raddle IC. Mechanism of antihypertensive action of prolonged administration of hydrochlorothiazide in rabbit and dog. Circulation Research, 1970;XXVII:717-25.