


Product Monograph - ASN-Fingolimod
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| Oral | Capsules / 0.5 mg fingolimod (as fingolimod hydrochloride) | Dibasic calcium phosphate, gelatin, magnesium stearate, titanium dioxide, iron oxide yellow. |
INDICATIONS AND CLINICAL USE
Adults: ASN-Fingolimod (fingolimod hydrochloride) is indicated as monotherapy for the treatment of patients with the relapsing-remitting form of multiple sclerosis (MS) to reduce the frequency of clinical exacerbations and to delay the progression of physical disability. ASN-Fingolimod is generally recommended in MS patients who have had an inadequate response to, or are unable to tolerate, one or more therapies for multiple sclerosis.
ASN-Fingolimod should only be prescribed by neurologists who are experienced in the treatment of multiple sclerosis, and are knowledgeable of the efficacy and safety profile of fingolimod and are able to discuss benefits/risks with patients.
Pediatrics (< 18 years of age): ASN-Fingolimod is not indicated in patients below 18 years of age.
Geriatrics (> 65 years of age): Clinical studies of fingolimod did not include sufficient numbers of patients aged 65 years and over to determine whether the safety and efficacy of fingolimod differs in elderly patients compared to younger patients. Physicians who choose to treat geriatric patients should consider that treatment with ASN-Fingolimod in the context of a greater frequency of reduced hepatic, renal, immune, pulmonary and cardiovascular function, other concomitant diseases and concomitant drug therapy warrants caution and may necessitate additional or more frequent monitoring (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
CONTRAINDICATIONS
- Patients who are hypersensitive to fingolimod or to any ingredient in the formulation of ASN-Fingolimod (fingolimod hydrochloride) or component of the container. For a complete listing, see the DOSAGE FORMS, COMPOSITION AND PACKAGING section of the product monograph.
- Patients with increased risk for opportunistic infections, including those who are immunocompromised due to treatment (e.g. antineoplastic, immunosuppressive or immunomodulating therapies, total lymphoid irradiation or bone marrow transplantation) or disease (e.g. immunodeficiency syndrome).
- Patients with severe active infections including active chronic bacterial, fungal or viral infections (e.g., hepatitis, tuberculosis).
- Patients with known active malignancies, except for patients with basal cell carcinoma.
- Patients with severe hepatic impairment (Child-Pugh Class C) (see WARNINGS AND PRECAUTIONS, Special Populations; WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; and ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
- Patients who in the last 6 months had myocardial infarction, unstable angina pectoris, stroke/transient ischemic attack, decompensated heart failure (requiring inpatient treatment), or New York Heart Association Class III/IV heart failure.
- Patients with severe cardiac arrhythmias requiring anti-arrhythmic treatment with Class Ia or Class III anti-arrhythmic drugs (see WARNINGS AND PRECAUTIONS).
- Patients with second-degree Mobitz type II atrioventricular (AV) block or third-degree AV block, or sick-sinus syndrome, if they do not have a pacemaker (see WARNINGS AND PRECAUTIONS).
- Patients with a baseline QTc interval ≥500 msec (see WARNINGS AND PRECAUTIONS).
- Women (including female adolescents) who are pregnant or of childbearing potential not using effective contraception (see WARNINGS AND PRECAUTIONS). Pregnancy must be excluded before start of treatment as ASN-Fingolimod may cause fetal harm.
WARNINGS AND PRECAUTIONS
Varicella vaccination
There have been very rare fatal cases of varicella zoster virus (VZV) infections in patients taking fingolimod (at recommended dose or higher doses used in clinical trials). These patients received prolonged concomitant corticosteroid use (more than 5 days) for treatment of multiple sclerosis relapses. Patients need to be assessed for their immunity to varicella (chickenpox) prior to ASN-Fingolimod treatment. It is recommended that patients without a health care professional confirmed history of chickenpox or documentation of a full course of vaccination with varicella vaccine undergo antibody testing to varicella zoster virus (VZV) before initiating ASN-Fingolimod therapy. A full course of vaccination for antibody- negative patients with varicella vaccine is recommended (if not contraindicated) prior to commencing treatment with ASN-Fingolimod. If vaccinated, treatment with ASN-Fingolimod should only be initiated 1 month after the patient has been vaccinated to allow full effect of vaccination to occur (see WARNINGS AND PRECAUTIONS, Herpetic infections).
SUMMARY OF IMPORTANT PRECAUTIONS TO BE TAKEN PRIOR TO INITIATING AND DURING TREATMENT WITH ASN-Fingolimod
Refer to the WARNINGS AND PRECAUTIONS – Immune, Cardiovascular, Ophthalmologic, Hepatic/Biliary/Pancreatic, Special Populations, DRUG INTERACTIONS, and TOXICOLOGY sections for more complete information.
ASN-Fingolimod should be used under the supervision of a neurologist experienced in the treatment of multiple sclerosis and familiar with the safety and efficacy of fingolimod capsules. All patients should have an electrocardiogram (ECG) performed prior to the first dose and 6 hours after the first dose. Patients should be monitored closely for signs and symptoms of bradyarrhythmia, with hourly pulse and blood pressure measurements, for at least 6 hours after the first dose.
Immune system effects
Fingolimod reduces circulating lymphocyte counts to 20-30% of baseline values via reversible retention in lymphoid organs and may increase the risk of infections.
- Delay the start of ASN-Fingolimod in patients with severe active infection until resolved.
- Check complete blood count (CBC) before starting therapy if no recent (i.e. within 6 months or after discontinuation of prior therapy) result is available.
- Instruct patients to promptly report symptoms of infection during treatment and for two months after discontinuation.
- Check varicella-zoster virus (VZV) antibody status before starting therapy if there is no health care professional confirmed history of chicken pox or vaccination with varicella vaccine; if negative, vaccination is recommended, with a delay in treatment initiation for 1 month after vaccination to allow full effect of vaccination to occur.
- Co-administration of anti-neoplastic, immunosuppressive or immune-modulating therapies is not recommended due to the risk of additive immune system effects.
Cardiovascular effects
Initiation of fingolimod treatment results in reversible heart rate decrease and has also been associated with atrioventricular (AV) conduction delays, including isolated cases of spontaneously resolving complete AV block (see WARNINGS AND PRECAUTIONS, Bradyarrhythmia; ADVERSE REACTIONS Post Market Adverse Events).
Conditions when ASN-Fingolimod should not be used
ASN-Fingolimod should not be used in patients with a history or currently experiencing sino-atrial heart block, a history of recurrent syncope or symptomatic bradycardia, significant QT prolongation (QTc >470 msec in adult females or >450 msec in adult males) (see CONTRAINDICATIONS) or in patients with relevant risk factors for QT prolongation (e.g. hypokalemia, hypomagnesemia or congenital QT prolongation), due to the risk of serious cardiac rhythm disturbances.
- ASN-Fingolimod should not be used in patients with a history of cardiac arrest, uncontrolled hypertension or severe untreated sleep apnea since significant bradycardia may be poorly tolerated in these patients. (see CONTRAINDICATIONS)
- ASN-Fingolimod should not be initiated in patients on concurrent therapy with beta-blockers, with heart-rate lowering calcium channel blockers or with other substances that may decrease heart rate because there is limited experience in situations of concomitant use and this may be associated with severe bradycardia and heart block. If treatment with ASN-Fingolimod is considered necessary, advice from a cardiologist should be sought regarding a switch to a non heart-rate-lowering drug or for appropriate monitoring (e.g., at least overnight monitoring) during treatment initiation, if such a switch cannot be implemented.
First dose monitoring of fingolimod
- For all patients, obtain an electrocardiogram (ECG) and measure blood pressure prior to and 6-hours after the first dose of fingolimod.
- Monitor all patients for signs and symptoms of bradyarrhythmia, with hourly pulse and blood pressure measurements, for at least 6 hours after the first dose.
- If symptoms of bradyarrhythmia or atrioventricular (AV) block occur, initiate appropriate management, with continued monitoring (e.g., continuous ECG monitoring) until the symptoms have resolved.
Should a patient require pharmacological intervention during the first dose observation period, continuous overnight monitoring (e.g., continuous ECG monitoring) in a medical facility should be instituted and the first dose monitoring strategy should be repeated when the second dose of fingolimod is administered.
The same precautions as for the first dose should be taken when patients are switched from the 0.25 mg to the 0.5 mg daily dose.
Extended monitoring, until the finding has resolved, is also required:
if the heart rate at 6 hours post-dose is <45 bpm or <60 bpm in pediatric patients aged 10 to below 12 years, or is the lowest value post-dose,
or
- if the ECG at 6 hours after the first dose shows new-onset second-degree or higher grade AV block.
If the ECG at 6 hours after the first dose shows a QTc interval ≥500 msec patients should be monitored overnight.
Fingolimod may lead to an increase in blood pressure. Measure blood pressure regularly in all patients.
Ophthalmologic effects
ASN-Fingolimod may cause macular edema with or without symptoms.
- An ophthalmic evaluation should be performed 3-4 months after treatment initiation in all patients, and at any time in any patient complaining of visual disturbances.
- Patients with diabetes mellitus or a history of uveitis are at increased risk of macular edema and should undergo an ophthalmic evaluation prior to initiating ASN-Fingolimod therapy and have regular ophthalmic evaluations while receiving ASN-Fingolimod therapy.
Hepatic effects
ASN-Fingolimod may increase liver transaminases.
- Obtain transaminase and bilirubin levels prior to initiating treatment if no recent (i.e. within the last 6 months) result is available, every 3 months during the first year of treatment and periodically thereafter in the absence of symptoms or when symptoms suggestive of hepatic injury develop.
Pregnancy
- ASN-Fingolimod is contraindicated in women (including female adolescents) who are pregnant or of childbearing potential not using effective contraception.
- Women of childbearing potential, including adolescent females, their parents (or legal representatives), and caregivers must be counselled on the potential for serious risk to the fetus and the need for effective contraception before treatment initiation, during, and for 2 months after treatment with ASN-Fingolimod.
---------------------------------------------------------------------------------------------------------------------
Cardiovascular
Initiation of fingolimod treatment is associated with decreased heart rate, PR interval prolongation and AV conduction delays, requiring patients to be monitored for at least 6 hours after receiving the first dose of ASN-Fingolimod (see WARNINGS AND PRECAUTIONS - Bradyarrhythmia; - PR Interval Prolongation and Atrioventricular [AV] Block; - Monitoring During Re-initiation of Therapy Following Discontinuation). Fingolimod capsules are also associated with QTc interval prolongation (see WARNINGS AND PRECAUTIONS - QTc interval prolongation).
Bradyarrhythmia
Decreased heart rate
Initiation of fingolimod treatment results in a reversible decrease in heart rate. After the first dose, the heart rate decrease is maximal within 6 hours post-dosing. The heart rate returns to baseline progressively over approximately one month during chronic treatment (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics – Heart rate and rhythm). Heart rates below 40 bpm in adults, and below 50 bpm in pediatric patients, were rarely observed (see ADVERSE REACTIONS). Adult patients who experienced bradycardia in controlled multiple sclerosis clinical trials were generally asymptomatic but some patients (0.5% receiving fingolimod capsules 0.5 mg and 0.2% of patients receiving placebo) experienced mild to moderate symptoms, including hypotension, dizziness, fatigue, palpitations, dyspnea, arrhythmia, and/or chest pain or chest discomfort, which resolved within the first 24 hours of treatment (see ADVERSE REACTIONS, ECG Findings and Bradyarrhythmia; DRUG INTERACTIONS, Pharmacodynamic Interactions, and ACTIONS AND CLINICAL PHARMACOLOGY, Pharmacodynamics – Heart rate and rhythm).
Conditions when ASN-Fingolimod should not be used
Clinical trials in patients with multiple sclerosis excluded patients with several cardiovascular conditions and/or risk factors. Due to limited experience in patients with cardiovascular conditions and/or risk factors and the known effects of fingolimod capsules on heart rate and cardiac conduction, ASN-Fingolimod should not be used in patients with the following conditions.
- ASN-Fingolimod should not be used in patients with a history or presence of sino-atrial heart block, a history of recurrent syncope or symptomatic bradycardia, or significant QT prolongation (QTc >470 msec in adult females or >450 msec in adult males) (see CONTRAINDICATIONS) or in patients with relevant risk factors for QT prolongation (e.g. hypokalemia, hypomagnesemia or congenital QT prolongation), due to the risk of serious cardiac rhythm disturbances. In patients for whom fingolimod is not contraindicated, if a decision is made to undertake treatment, such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring strategy, which should be at least overnight.
- ASN-Fingolimod should not be used in patients with a history of cardiac arrest, uncontrolled hypertension or severe untreated sleep apnea because significant bradycardia may be poorly tolerated in these patients (see CONTRAINDICATIONS). In patients for whom fingolimod is not contraindicated, if a decision is made to undertake treatment, such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring, strategy which should be at least overnight.
Fingolimod capsules have not been studied in patients with arrhythmias requiring treatment
- with Class Ia (e.g. quinidine, disopyramide) or Class III (e.g. amiodarone, sotalol) antiarrhythmic drugs. Class Ia and Class III antiarrhythmic drugs have been associated with cases of torsades de pointes in patients with bradycardia (see CONTRAINDICATIONS).
- There is limited experience with fingolimod capsules in patients receiving concurrent therapy with beta blockers, heart-rate lowering calcium channel blockers (such as verapamil or diltiazem), or other substances that may decrease heart rate (e.g. digoxin, cholinesterase inhibitors or pilocarpine). Since the initiation of fingolimod treatment is also associated with bradycardia (see “Decreased Heart Rate”), concomitant use of these substances during ASN-Fingolimod initiation may be associated with severe bradycardia and heart block. Because of the potential additive effect on heart rate, ASN-Fingolimod should not be initiated in patients who are concurrently treated with these substances. If treatment with ASN-Fingolimod is considered necessary, advice from a cardiologist should be sought regarding a switch to drugs that do not lower heart rate or for appropriate monitoring (e.g., at least overnight monitoring) during treatment initiation, if the heart-rate-lowering drugs cannot be discontinued (see DRUG INTERACTIONS).
For patients with any of the above conditions, treatment should only be considered if the expected benefits outweigh the known risks.
First dose monitoring of fingolimod
- For all patients, obtain an ECG and measure blood pressure prior to and 6-hours after the first dose.
- Monitor all patients for signs and symptoms of bradyarrhythmia, with hourly pulse and blood pressure measurements, for at least 6 hours after the first dose.
- If symptoms of bradyarrhythmia or AV block occur, initiate appropriate management, with continued monitoring (e.g., continuous ECG monitoring) until the symptoms have resolved.
- Should a patient require pharmacological intervention during the first-dose observation period, continuous overnight monitoring (e.g., continuous ECG monitoring) in a medical facility should be instituted and the first-dose monitoring strategy should be repeated when the second dose of fingolimod is administered.
The same precautions as for the first dose should be taken when patients are switched from the 0.25 mg to the 0.5 mg daily dose.
Extended monitoring, until the finding has resolved, is also required
if the heart rate at 6 hours post-dose is <45 bpm or is the lowest value post-dose (suggesting that the maximum pharmacodynamic effect on the heart has not yet manifested)
or
- if the ECG at 6 hours after the first dose shows new-onset second-degree or higher grade AV block.
If the ECG at 6 hours after the first dose shows a QTc interval ≥500 msec patients should be monitored overnight.
PR Interval Prolongation and Atrioventricular (AV) Block
Initiation of fingolimod treatment has been associated with PR interval prolongation and AV conduction delays. The maximum increase in the PR interval occurs at about 6 h post-dosing. In Phase III controlled clinical trials in adults, the incidence of first degree AV block on ECG at 6 h after the first dose was 4.7% of patients receiving fingolimod 0.5 mg and 1.5% of patients receiving placebo, while the incidence of 2nd-degree AV block Mobitz type 1 was 0.2% for fingolimod 0.5 mg and 0 for placebo. On Holter monitoring 2nd-degree AV block, Mobitz type 1 (Wenckebach), was reported in 3.4% of patients receiving fingolimod 0.5 mg and 2% of patients on placebo, while 2:1 AV block was reported in 1.7% of patients receiving fingolimod 0.5 mg, but not in any patients receiving placebo. The conduction abnormalities typically were transient, asymptomatic, and resolved within the first 24-hours on treatment. Isolated cases of transient, spontaneously resolving complete AV block have been reported during post-marketing use of fingolimod (see ADVERSE REACTIONS, ECG Findings and Bradyarrhythmia; DRUG INTERACTIONS, Pharmacodynamic Interactions; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics – Heart rate and rhythm).
Monitoring During Re-initiation of Therapy Following Discontinuation
If fingolimod therapy is discontinued for more than 2 weeks, after the first month of treatment, the effects on heart rate and AV conduction may recur on reintroduction of fingolimod treatment and the same precautions as for the first dose should apply (i.e., monitor for at least 6 hours after the first dose). Within the first 2 weeks of treatment, first-dose procedures are recommended after an interruption of one day or more. During weeks 3 and 4 of treatment, first dose procedures are recommended after a treatment interruption of more than 7 days.
QTc Prolongation
Fingolimod is associated with QTc interval prolongation (see ADVERSE REACTIONS, ECG Findings; DRUG INTERACTIONS, Pharmacodynamic Interactions; and ACTIONS AND CLINICAL PHARMACOLOGY, Pharmacodynamics – Thorough QT Study).
In a thorough QT interval study of doses of 1.25 mg or 2.5 mg fingolimod at steady-state, when a negative chronotropic effect of fingolimod was still present, fingolimod treatment resulted in a prolongation of QTcI, with the upper limit of the 90% CI ≤13.0 ms. In the multiple sclerosis studies, clinically relevant effects on prolongation of the QTc-interval have not been observed. However, patients at risk for QT prolongation were excluded from clinical studies.
Since initiation of fingolimod treatment results in decreased heart rate, and therefore a prolongation of the QT interval, fingolimod should not be used in patients with significant QT prolongation (QTc >470 msec in adult females or >450 msec in adult males) or in patients with relevant risk factors for QT prolongation (e.g., hypokalemia, hypomagnesemia or congenital QT prolongation).
If a decision is made to undertake treatment, such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring, which should be at least overnight.
Fingolimod has not been studied in patients treated with drugs that prolong the QT interval. Because the risk of QT interval prolongation is expected to be greater in patients who receive concomitant treatment with other drugs that prolong the QT interval, the use of ASN-Fingolimod with such drugs should be avoided. If a decision is made to undertake treatment such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring, which should be at least overnight.
Many drugs that cause QTc prolongation are suspected to increase the risk of torsade de pointes, a polymorphic ventricular tachyarrhythmia. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Blood pressure effects
In multiple sclerosis clinical trials, patients treated with fingolimod 0.5 mg had an average increase of approximately 2 mmHg in systolic pressure, and approximately 1 mmHg in diastolic pressure, first detected after approximately 1 month of treatment initiation, and persisting with continued treatment. In controlled studies involving 854 multiple sclerosis adult patients on fingolimod 0.5 mg and 511 multiple sclerosis patients on placebo, hypertension was reported as an adverse reaction in 5% of patients on fingolimod 0.5 mg and in 3% of patients on placebo. Blood pressure should be monitored during treatment with fingolimod.
Immune
Infections
A core pharmacodynamic effect of fingolimod is a dose-dependent reduction of peripheral lymphocyte count to 20-30% of baseline values. This is due to the reversible sequestration of lymphocytes in lymphoid tissues. Because elimination of fingolimod after discontinuation of ASN-Fingolimod may take up to 2 months, recovery of peripheral lymphocyte counts to baseline values is gradual (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics). ASN-Fingolimod may therefore increase the risk of infections, including opportunistic infections (see ADVERSE REACTIONS) during treatment and for up to 2 months after discontinuation of treatment. Continue monitoring for infections during this period.
ASN-Fingolimod is contraindicated in patients at an increased risk of opportunistic infections and in patients with severe active infections including active chronic bacterial, fungal or viral infections (see CONTRAINDICATIONS).
Before initiating and during treatment with ASN-Fingolimod, the following precautions should be taken:
- Obtain a CBC before initiating treatment if no recent (i.e. within 6 months or after discontinuation of prior therapy) result is available. Treatment with ASN-Fingolimod should not be initiated when lymphocyte counts are consistently below the normal range.
- Treatment should not be initiated when there are signs and symptoms of a severe active bacterial, fungal or viral infection. Instruct patients to promptly report symptoms or signs suggestive of any infection, during and for up to 2 months after discontinuation of treatment, to facilitate early diagnosis and initiation of appropriate treatments (see WARNINGS AND PRECAUTIONS, Patient Counseling Information).
- Determine immunization status for VZV. Patients need to be assessed for their immunity to varicella (chickenpox) prior to ASN-Fingolimod treatment. It is recommended that patients without a health care professional confirmed history of chickenpox or documentation of a full course of vaccination with varicella vaccine undergo antibody testing to varicella zoster virus (VZV) before initiating ASN-Fingolimod therapy. A full course of vaccination for antibody-negative patients with varicella vaccine is recommended prior to commencing treatment with ASN-Fingolimod, if not contraindicated (see ADVERSE DRUG REACTIONS). For patients requiring vaccination, initiation of treatment with ASN-Fingolimod should be delayed for 1 month after the patient has been vaccinated, to allow the full effect of the vaccination to occur (see WARNINGS AND PRECAUTIONS, Varicella Zoster Vaccination; WARNINGS AND PRECAUTIONS, Vaccination).
In the 24-month placebo controlled multiple sclerosis clinical trial in adults, the overall rate of infections (72%) and serious infections (2%) with fingolimod 0.5 mg was similar to that of placebo. However, bronchitis and pneumonia were more common in fingolimod hydorhcloride-treated patients (see ADVERSE REACTIONS).
Physicians should advise patients about the potential for increased risk of infections and necessary vigilance during treatment and after discontinuation of treatment with ASN-Fingolimod (see WARNINGS AND PRECAUTIONS, Immune System Effects Following Discontinuation of Treatment). For patients who develop serious infections, suspending treatment with ASN-Fingolimod should be considered, and the benefits and risks of treatment should be re-assessed prior to re- initiation of treatment.
Herpetic infections
Two adult patients died of herpetic infections during controlled trials. One death was due to a disseminated primary varicella zoster infection and the other to herpes simplex encephalitis. In both cases, the patients were taking a 1.25 mg dose of fingolimod (higher than the recommended
0.5 mg dose) and had received prolonged (more than 5 days) concomitant corticosteroid therapy to treat suspected MS relapses.
Serious, life-threatening events of disseminated varicella zoster and herpes simplex infections, including cases of encephalitis and multiorgan failure, have occurred with fingolimod 0.5 mg in the post-marketing setting. One of these events, disseminated reactivation of varicella zoster virus in a patient that received prolonged concomitant corticosteroid therapy, was fatal.
Physicians should be vigilant for clinical symptoms that may be suggestive of serious herpetic infections. Disseminated herpetic infections should be included in the differential diagnosis when patients who are receiving fingolimod present with an atypical MS relapse or multiorgan failure. For cases of disseminated herpetic infections, antiviral therapy and discontinuation of ASN-Fingolimod treatment is recommended. Treatment of zoster should follow current relevant guidelines.
Progressive Multifocal Leukoencephalopathy (PML)
Cases of progressive multifocal leukoencephalopathy (PML), some of which have been fatal, have been reported in the post-marketing setting (see ADVERSE REACTIONS). PML is an opportunistic infection caused by JC virus (JCV) that typically only occurs in patients who are immunocompromised, which may be fatal or result in severe disability. In some of the reported cases, PML has occurred in patients who were not previously treated with natalizumab, which has a known association with PML, and in patients who had not previously taken or were not concomitantly taking any immunosuppressive or immunomodulatory medications. Other ongoing systemic medical conditions resulting in compromised immune system function were not reported in most of these cases. These cases of PML have occurred after approximately 2-3 years of treatment. The relationship between the risk of PML and duration of treatment is not known. The incidence rate for PML appears to be higher for patients in Japan; the reasons are currently unknown.
Physicians should be vigilant for clinical symptoms or MRI findings that may be suggestive of PML. If PML is suspected, fingolimod treatment should be suspended until PML has been excluded. Typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes.
MRI findings suggestive of PML may be apparent before clinical signs or symptoms. Cases of PML, diagnosed based on MRI findings and the detection of JCV DNA in the cerebrospinal fluid in the absence of clinical signs or symptoms specific to PML, have been reported in patients treated with MS medications associated with PML, including fingolimod. Many of these patients subsequently became symptomatic with PML. Therefore, monitoring with MRI for signs that may be consistent with PML may be useful, and any suspicious findings should lead to further investigation to allow for an early diagnosis of PML, if present. Before initiating treatment with ASN-Fingolimod, a recent MRI should be available. During routine MRI (in accordance with national and local recommendations), physicians should pay attention to PML suggestive lesions. Lower PML-related mortality and morbidity have been reported following discontinuation of another MS medication associated with PML in patients with PML who were initially asymptomatic compared to patients with PML who had characteristic clinical signs and symptoms at diagnosis. It is not known whether these differences are due to early detection and discontinuation of MS treatment or due to differences in disease in these patients.
Cryptococcal Meningitis
Cases of cryptococcal meningitis have been reported in the post-marketing setting, generally after approximately 2-3 years of treatment, but may occur earlier. The relationship between the risk of cryptococcal infection and the duration of treatment is not known (see ADVERSE REACTIONS). Some cases of cryptococcal meningitis have been fatal. Patients with symptoms and signs consistent with cryptococcal meningitis should undergo prompt diagnostic evaluation and appropriate treatment should be initiated if cryptococcal meningitis is diagnosed.
Human papilloma virus
Human papilloma virus (HPV) infection, including papilloma, dysplasia, warts and HPV-related cancer, has been reported under treatment with ASN-Fingolimod in the post-marketing setting (see ADVERSE REACTIONS). Due to the immunosuppressive properties of fingolimod, vaccination against HPV should be considered prior to treatment initiation with ASN-Fingolimod taking into account vaccination recommendations. Cancer screening, including Pap test, is recommended as per standard of care.
Vaccination
- The use of live attenuated vaccines during ASN-Fingolimod treatment and for two months after discontinuing treatment is not recommended due to the risk of infection from the vaccine (see WARNINGS AND PRECAUTIONS, Infections).
- Vaccination may be less effective during and for up to two months after discontinuing treatment with ASN-Fingolimod (see WARNINGS AND PRECAUTIONS, Immune System Effects Following Discontinuation of Treatment; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Immune system).
- For patients with negative IgG antibody test results for VZV due to no previous exposure or vaccination and who do not have contraindications for the vaccine, a full course of vaccination with varicella vaccine is recommended prior to commencing treatment with fingolimod. Initiation of ASN-Fingolimod therapy should be postponed for one month after vaccination to allow the full effect of vaccination to occur (see WARNINGS AND PRECAUTIONS, Varicella Zoster Vaccination).
- The immunization recommendations for adults (routine and specific risk groups) from the National Advisory Committee on Immunization (NACI) (http://www.phac-aspc.gc.ca/im/is- cv/index-eng.php) and local infectious disease experts should be considered when evaluating the need for other vaccinations, before commencing and during treatment with ASN-Fingolimod.
Immune System Effects Following Discontinuation of Treatment
If a decision is made to stop treatment with ASN-Fingolimod, the physician and patient need to be aware that fingolimod remains in the blood and has pharmacodynamic effects, such as decreased lymphocyte counts for up to two months, following the last dose. Lymphocyte counts typically return to the normal range within 2 months of stopping therapy (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Immune system). Physicians should advise patients about the potential for increased risk of infections and necessary vigilance for up to two months after discontinuation of treatment with ASN-Fingolimod.
Because of the continuing pharmacodynamic effects of fingolimod, starting other therapies during the 2 months following stopping ASN-Fingolimod warrants the same precautions as concomitant treatment with ASN-Fingolimod. Use of immunosuppressants soon after the discontinuation of ASN-Fingolimod may lead to an additive effect on the immune system and, therefore, caution should be applied (see DRUG INTERACTIONS and WARNINGS AND PRECAUTIONS, Return of disease activity (rebound) and severe increase in disability after ASN-Fingolimod discontinuation).
Prior and Concomitant Treatment with Antineoplastic, Immunosuppressive or Immune- modulating Therapies
Co-administration of anti-neoplastic, immunosuppressive or immune-modulating therapies is not recommended due to the risk of additive immune system effects (see DRUG INTERACTIONS). For the same reason, corticosteroids should be co-administered with caution and specific decisions as to the dosage and duration of concomitant treatment should be based on clinical judgment. Co-administration of a short course of corticosteroids (up to 5 days as per study protocols) did not increase the overall rate of infection in patients treated with fingolimod in the Phase III clinical trials, compared to placebo.
When switching to or from another disease modifying therapy with immunosuppressive or immune modulating effects, the half-life and mode of action of ASN-Fingolimod and the other therapy must be considered in order to avoid an additive immune effect whilst at the same time minimizing risk of disease reactivation. Prior to initiating the new treatment, a recent CBC should be available to ensure any immune effects (e.g. cytopenia) of the discontinued therapy have resolved.
Beta interferon, glatiramer acetate or dimethyl fumarate
ASN-Fingolimod can generally be started immediately after discontinuation of beta interferon, glatiramer acetate or dimethyl fumarate provided that immune effects (e.g. cytopenia) from these therapies have resolved.
Natalizumab or teriflunomide
Elimination of natalizumab usually takes up to 2-3 months following discontinuation. Without an accelerated elimination procedure, clearance of teriflunomide from plasma can take several months (average: 8 months) and up to 2 years. Due to the long half-life of natalizumab or teriflunomide, caution regarding potential additive immune effects is required when switching patients from these therapies to ASN-Fingolimod. A careful case-by-case assessment regarding the timing of the initiation of ASN-Fingolimod treatment is recommended.
Alemtuzumab
Due to the characteristics and duration of alemtuzumab immune suppressive effects described in its Product Monograph, initiating treatment with ASN-Fingolimod after alemtuzumab is not recommended unless the benefits of ASN-Fingolimod treatment clearly outweigh the risks for the individual patient.
Hepatic/Biliary/Pancreatic
Liver function
Increased hepatic enzymes, mostly alanine aminotransaminase (ALT) elevation, have been reported in multiple sclerosis patients treated with fingolimod. In clinical trials, a 3-fold the upper limit of normal (ULN) or greater elevation in ALT occurred in 8% of adult patients treated with fingolimod 0.5 mg, as compared to 2% of patients on placebo. Elevations 5-fold the ULN occurred in 2% of patients on fingolimod 0.5 mg and 1% of patients on placebo. In clinical trials, fingolimod was discontinued if the elevation exceeded 5 times the ULN. Recurrence of ALT elevations occurred with re-challenge in some patients, supporting a relationship to fingolimod. The majority of elevations occurred within 6-9 months of initiating treatment and serum transaminase levels returned to normal within approximately 2 months after discontinuation of fingolimod (see ADVERSE REACTIONS, Abnormal Hematologic and Clinical Chemistry Findings-Liver function).
For all patients, recent (i.e. within last 6 months) transaminase and bilirubin levels should be available before initiation of treatment with ASN-Fingolimod. During treatment, liver enzymes should be evaluated every 3 months for the first year and periodically thereafter. If liver transaminases rise above 5 times the ULN, more frequent monitoring should be instituted, including serum bilirubin and alkaline phosphatase (ALP) measurement. With repeated confirmation of liver transaminases above 5 times the ULN, treatment with ASN-Fingolimod should be interrupted and only re-commenced once liver transaminase values have normalized. The benefits and risks of treatment should be re-assessed prior to re-initiation of treatment.
Patients who develop symptoms suggestive of hepatic dysfunction, such as unexplained vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine during treatment, should have liver enzymes checked and ASN-Fingolimod should be discontinued if significant liver injury is confirmed (see ADVERSE REACTIONS, Abnormal Hematologic and Clinical Chemistry Findings, Liver function).
Patients with pre-existing liver disease may be at an increased risk of developing elevated liver enzymes during ASN-Fingolimod treatment (see WARNINGS AND PRECAUTIONS, Special Populations; ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
Neoplasm
For patients treated with immunosuppressive or immune modulating drugs there is potential for an increased risk of lymphomas and other malignancies, particularly of the skin.
Lymphoma
Cases of lymphoma, mainly Non-Hodgkin’s Lymphoma, including both T-cell and B-cell types and CNS lymphoma, have been reported in clinical trials and in the post-marketing setting with fingolimod (see ADVERSE REACTIONS). The cases reported were heterogeneous in nature. The incidence of lymphoma (B-cell and T-cell) cases was higher in clinical trials than expected in the general population. Cutaneous T-cell lymphoma (including mycosis fungoides) has been reported with fingolimod in the post-market setting (see ADVERSE REACTIONS).
Basal cell carcinoma and other cutaneous neoplasms
Basal cell carcinoma (BCC) and other cutaneous neoplasms, including malignant melanoma, squamous cell carcinoma, Merkel cell carcinoma and Kaposi’s sarcoma have been reported in patients receiving fingolimod (see ADVERSE REACTIONS). Vigilance for cutaneous neoplasms is recommended in patients receiving fingolimod. Health care professionals and patients are advised to monitor for suspicious skin lesions before initiating treatment and regularly during treatment with ASN-Fingolimod, particularly for patients with risk factors for skin cancer. If a suspicious skin lesion is observed, it should be promptly evaluated.
Since there is a potential risk of malignant skin growths, patients treated with ASN-Fingolimod should be cautioned against exposure to sunlight and ultraviolet light by wearing protective clothing and using a sunscreen with a high protection factor. These patients should not receive concomitant phototherapy with UV-B-radiation or PUVA-photochemotherapy.
Neurologic
Posterior reversible encephalopathy syndrome
Rare cases of posterior reversible encephalopathy syndrome (PRES) have been reported in adults at 0.5 mg dose in clinical trials and in the post-marketing setting. Symptoms reported included sudden onset of severe headache, nausea, vomiting, altered mental status, visual disturbances and seizure; status epilepticus has been reported in association with PRES. Symptoms of PRES are usually reversible but may evolve into ischemic stroke or cerebral hemorrhage. Delay in diagnosis and treatment may lead to permanent neurological sequelae. If PRES is suspected, ASN-Fingolimod should be discontinued.
Tumefactive lesions
Cases of tumefactive lesions associated with MS relapse have been reported in the post- marketing setting. In case of severe relapses, MRI should be performed to exclude tumefactive lesions. Discontinuation of ASN-Fingolimod should be considered by the physician on a case-by-case basis taking into account individual benefits and risks.
Return of disease activity (rebound) and severe increase in disability after fingolimod discontinuation
Severe increase in disability accompanied by multiple new lesions on MRI has been reported after discontinuation of fingolimod in the postmarketing setting. Patients in most of these reported cases did not return to the functional status they had before stopping fingolimod. The increase in disability generally occurred within 12 weeks after stopping fingolimod, but was reported up to and beyond 24 weeks after fingolimod discontinuation. Therefore, caution is indicated when stopping ASN-Fingolimod therapy. Monitor patients for development of high disease activity and severe increase in disability following discontinuation of ASN-Fingolimod and begin appropriate treatment as needed.
Seizures
Caution should be exercised when administering ASN-Fingolimod to patients with pre-existing seizure disorder. In the pivotal adult studies, cases of seizures were reported at a greater incidence for fingolimod-treated patients compared to their respective control arms (see ADVERSE REACTIONS, Clinical Trials Adverse Reactions). It is not known whether these events were related to the effects of MS alone, to fingolimod, or to a combination of both.
Ophthalmologic
Macular Edema
Macular edema (see ADVERSE REACTIONS, Macular edema) with or without visual symptoms has been reported in 0.4% of adult patients treated with fingolimod 0.5 mg compared to 0.1% of patients receiving placebo. Macular edema was diagnosed predominantly in the first 3-4 months of therapy. Some patients presented with blurred vision or decreased visual acuity, but others were asymptomatic and diagnosed on routine ophthalmic examination. Macular edema generally improved or resolved with or without treatment after drug discontinuation, but some patients had residual visual acuity loss even after resolution of macular edema. In clinical trials, treatment with fingolimod was discontinued when patients developed macular edema and was not re-initiated when the adverse event resolved.
An ophthalmic evaluation is recommended 3-4 months after treatment initiation. If patients report visual disturbances at any time while on ASN-Fingolimod therapy, an evaluation of the fundus, including the macula, should be carried out (see WARNINGS AND PRECAUTIONS, Patient Counseling Information).
It is recommended that ASN-Fingolimod be discontinued if a patient develops macular edema. Continuation of treatment in patients with macular edema has not been evaluated. A decision on whether or not ASN-Fingolimod therapy should be re-initiated after resolution of macular edema needs to take into account the potential benefits and risks for the individual patient.
Macular edema in patients with history of uveitis or diabetes mellitus
Patients with a history of uveitis and patients with diabetes mellitus are at increased risk of macular edema (see ADVERSE REACTIONS, Macular edema). Multiple sclerosis patients with concomitant diabetes mellitus were excluded from the clinical trials with fingolimod. In other clinical trials with fingolimod that included diabetic patients, the rate of macular edema was several-fold greater in diabetic patients compared to non-diabetic patients, and macular edema was twice as frequent in patients treated with fingolimod (diabetic and non-diabetic) compared to patients receiving control treatment.
In addition to an ophthalmic evaluation prior to initiating ASN-Fingolimod therapy and at 3-4 months after initiating treatment, regular follow-up evaluations are recommended for multiple sclerosis patients with diabetes mellitus or a history of uveitis while receiving ASN-Fingolimod therapy.
Respiratory
Dose-dependent reductions in forced expiratory volume over 1 second (FEV1) and diffusion lung capacity for carbon monoxide (DLCO) were observed in patients treated with fingolimod as early as 1 month after treatment initiation (see ADVERSE REACTIONS, Respiratory). The changes in FEV1 appear to be reversible after treatment discontinuation, but there is insufficient information to determine the reversibility of the decrease of DLCO after drug discontinuation.
Spirometric evaluation of respiratory function and evaluation of DLCO should be performed during therapy with ASN-Fingolimod if clinically indicated.
Multiple sclerosis patients with compromised respiratory function (e.g., pulmonary fibrosis, diagnosis of active pulmonary disease, abnormal pulmonary function tests) were excluded from fingolimod clinical trials.
ASN-Fingolimod should be used with caution in patients with severe respiratory disease, pulmonary fibrosis, moderate and severe asthma or chronic obstructive pulmonary disease (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Pulmonary Function).
Metabolic
Total Cholesterol, LDL Cholesterol, and Triglycerides
ASN-Fingolimod treatment results in increased levels of total cholesterol, LDL cholesterol, and triglycerides (see ADVERSE REACTIONS, Cholesterol and Triglycerides). These observations should be taken into consideration when treating patients with pre-existing hyperlipidemia, atherosclerosis, or ischemic heart disease.
Psychiatric
Depression and Suicidal Ideation:
Depression and suicidal ideation are known to occur at an increased frequency in the MS population. A relationship between the occurrence of depression and/or suicidal ideation and the use of fingolimod in the MS population has not been established. Patients, families and caregivers of patients being treated with ASN-Fingolimod should be advised to monitor for the emergence of any symptoms of depression and/or suicidal ideation and report such symptoms immediately to healthcare providers, for prompt evaluation.
Sexual Function/Reproduction
Labor and delivery
There are no data on the effects of fingolimod on labor and delivery.
Infertility
Data from preclinical studies does not suggest that fingolimod would be associated with an increased risk of reduced fertility.
Female reproductive toxicity
Based on animal data, fingolimod is potentially teratogenic (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, Special Populations-Pregnant women).
Male reproductive toxicity
Available data do not suggest that fingolimod would be associated with an increased risk of male-mediated fetal toxicity.
Special Populations
Women of childbearing potential / Contraception: ASN-Fingolimod is contraindicated in women (including female adolescents) who are pregnant or of childbearing potential not using effective contraception (see CONTRAINDICATIONS). Therefore, before initiation of ASN-Fingolimod treatment in women of childbearing potential, a negative pregnancy test result must be available and counselling should be provided regarding the serious risk to the fetus. Women of childbearing potential must use effective contraception during treatment and for 2 months after discontinuation of ASN-Fingolimod, since fingolimod takes approximately 2 months to eliminate from the body after treatment discontinuation (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Immune system). If the woman becomes pregnant while taking this drug, the patient must be apprised of the risk to the fetus.
Pregnant Women: ASN-Fingolimod is contraindicated in women (including female adolescents) who are pregnant or of childbearing potential not using effective contraception (see CONTRAINDICATIONS). There are no adequate and well-controlled studies in pregnant women.
Available human data (post-marketing data and pregnancy registry information) suggest that use of fingolimod is associated with an increased risk of overall major congenital malformation (approximately 5%) when administered during pregnancy in comparison with the prevalence observed in the general population (2-4%).
The pattern of malformation reported for fingolimod is similar to that observed in the general population, however, increased prevalence of the following specific major malformations were noted:
- Congenital heart disease such as atrial septal defects
- Renal abnormalities
- Musculoskeletal abnormalities
If a female becomes pregnant while taking ASN-Fingolimod, treatment must be discontinued.
ASN-Fingolimod must be discontinued 2 months before planning a pregnancy. Medical advice should be given regarding the risk of harmful effects on the fetus associated with treatment and medical follow-up examination should be performed (e.g. ultrasonography examination). Also, the possibility of severe exacerbation of disease should be considered in females discontinuing ASN-Fingolimod because of pregnancy or planned pregnancy, and patients should consult their physicians on potential alternatives (see WARNINGS AND PRECAUTIONS, Return of disease activity (rebound) and severe increase in disability after ASN-Fingolimod discontinuation and Immune System Effects Following Discontinuation of Treatment).
Animal studies have shown that fingolimod induced reproductive toxicity including fetal loss and teratogenicity when given to pregnant animals. When fingolimod was administered orally to pregnant rats during the period of organogenesis, increased incidences of fetal malformations and embryo-fetal lethality were observed starting at doses corresponding to 2 times the exposure in humans at the recommended dose of 0.5 mg. The most common fetal visceral malformations in rats included persistent truncus arteriosus and ventricular septal defect. Oral administration of fingolimod to pregnant rabbits during organogenesis resulted in increased incidences of embryo- fetal lethality and fetal growth retardation starting at doses similar to the exposure in humans at the recommended dose of 0.5 mg (see TOXICOLOGY).
Pregnancy Exposure: There is a registry that monitors pregnancy outcomes in women exposed to ASN-Fingolimod during pregnancy. If a patient becomes pregnant while taking ASN-Fingolimod, physicians are encouraged to report this event by calling Ascend Laboratories Ltd. at +1-833-974-0018.
Nursing Women: Fingolimod is excreted in the milk of animals treated during lactation. There is no data on the effects of fingolimod on the breastfed child or the effects of fingolimod on milk production. Since many drugs are excreted in human milk and because of the potential for serious adverse drug reactions to fingolimod in nursing infants, women receiving ASN-Fingolimod should not breast feed.
Hepatic Impairment: ASN-Fingolimod is contraindicated in patients with severe hepatic impairment (Child-Pugh Class C) (see CONTRAINDICATIONS). Although no dose adjustments are needed in patients with mild or moderate hepatic impairment, caution should be exercised when initiating treatment with ASN-Fingolimod in these patients (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics - Special Populations and Conditions).
Patients with pre-existing liver disease were excluded from MS clinical trials and it is not known if these patients are at an increased risk of developing elevated liver function tests, more severe liver injury, or other adverse events during treatment with ASN-Fingolimod (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Renal Impairment: Caution is recommended when using ASN-Fingolimod in patients with severe renal impairment (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics - Special Populations and Conditions).
Pediatrics (< 18 years of age): ASN-Fingolimod is not indicated for use in pediatric patients (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics - Special Populations and Conditions).
Geriatrics (> 65 years of age): Clinical studies of fingolimod did not include sufficient numbers of patients aged 65 years and over to assess efficacy and safety in this age group. Due to the greater frequency of reduced hepatic, renal, immune, pulmonary and cardiovascular function, other concomitant diseases and concomitant drug therapy, treatment with fingolimod merits caution and may necessitate additional or more frequent monitoring in geriatric patients (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Patient Counseling Information
Patients receiving ASN-Fingolimod should also be given the following information by the physician and /or pharmacist:
- 1.
General
Summarize for patients the benefits and potential risks of treatment with ASN-Fingolimod.
Tell patients to take ASN-Fingolimod once daily as prescribed. Tell patients not to discontinue ASN-Fingolimod without first discussing this with the prescribing physician.
- 2.
First-dose cardiovascular effects and monitoring
Advise patients that initiation of fingolimod treatment results in a decrease in heart rate. Inform patients that they will need to have their heart rate and blood pressure monitored in the doctor's office or other medical facility for at least 6 hours after the first dose, and that they will be required to have an ECG performed prior to dosing and at the end of the 6-hour monitoring period. Also inform patients that in case of abnormal ECG recording, very slow heart rate at the end of the 6-hour observation period, or symptoms of bradyarrhythmia they will need to be monitored longer, possibly overnight, until findings have resolved. Symptoms of bradyarrhythmia may include dizziness or palpitations. Advise patients that if fingolimod is discontinued for more than two weeks, effects similar to those observed on treatment initiation may be seen and observation for at least 6 hours, including periodic assessment of heart rate, will be needed on treatment re-initiation.
- 3.
Risk of Infections
Inform patients that they may be more likely to get infections when taking ASN-Fingolimod, and that they should contact their physician if they develop symptoms of infection. Advise patients that there is the potential for additive immune system effects if corticosteroid therapy is required. Advise patients that the use of some vaccines should be avoided during treatment with ASN-Fingolimod and for 2 months after discontinuation. Advise patients who have not had chickenpox or vaccination with varicella vaccine that the vaccination is recommended prior to commencing treatment with ASN-Fingolimod.
- 4.
Blood pressure increase
Advise patients that an increase in blood pressure could occur during chronic treatment with ASN-Fingolimod and that regular monitoring of blood pressure should be undertaken.
- 5.
Liver enzyme increases
Inform patients that ASN-Fingolimod may increase liver enzymes. Advise patients that regular blood testing will be performed and that they should contact their physician if they have any unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, or jaundice and/or dark urine during treatment.
- 6.
Macular edema
Advise patients that ASN-Fingolimod may cause macular edema, and that they should contact their physician if they experience any changes in their vision. Inform patients with diabetes mellitus or a history of uveitis that their risk of macular edema is increased.
- 7.
Respiratory effects
Advise patients that they should contact their physician if they experience new onset or worsening dyspnea.
- 8.
Fetal risk
ASN-Fingolimod has been shown to be potentially teratogenic in animal studies. It is contraindicated in women of childbearing potential (including female adolescents) not using effective contraception and in pregnant women.
- A negative pregnancy test must be confirmed prior to starting treatment, and it must be repeated at suitable intervals.
- Women of childbearing potential, including adolescent females, their parents (or legal representatives), and caregivers must be counselled before treatment initiation and regularly thereafter about the serious risks of ASN-Fingolimod to the fetus.
- Women of childbearing potential must use effective contraception during treatment and for two months following treatment discontinuation.
- While on treatment, females must not become pregnant. If a patient becomes pregnant while on treatment, ASN-Fingolimod must be discontinued. When stopping ASN-Fingolimod treatment due to pregnancy or for planning a pregnancy, the possible return of disease activity should be considered. Medical advice must be given regarding the risk of harmful effects to the fetus associated with ASN-Fingolimod treatment and ultrasonography examinations should be performed.
- ASN-Fingolimod must be stopped 2 months before planning a pregnancy.
- 9.
Drug interactions
Advise patients that concomitant use of certain cardiac medications may increase the risk of bradyarrhythmia with first-dose administration of ASN-Fingolimod and ask them to provide information on all medications currently being taken.
Advise patients that co-administration of anti-neoplastic, immunosuppressive or immune-modulating therapies is not recommended due to the risk of additive immune system effects.
- 10.
Persistence of ASN-Fingolimod effects after drug discontinuation
Advise patients that ASN-Fingolimod remains in the blood and continues to have effects, including decreased blood lymphocyte counts, for up to 2 months following the last dose.
- 11.
Risk of skin cancer
Inform patients that cases of skin cancers have been reported in MS patients treated with fingolimod therefore, patients should monitor and report any suspicious lesion before treatment initiation and during ASN-Fingolimod treatment. Advise patients to limit their exposure to sunlight and UV rays through appropriate protective clothing and application of sunscreen with a high degree of UV protection.
- 12.
Cases of PML
Inform patients that cases of progressive multifocal leukoencephalopathy (PML) have occurred after approximately 2-3 years of monotherapy treatment although an exact relationship with the duration of treatment is unknown.
- 13.
Risk of return of disease activity and severe increase in disability
Inform patients that after ASN-Fingolimod treatment is stopped, symptoms of MS can return and may become worse compared to before or during treatment. Advise patients that they should contact their physician if their MS symptoms get worse after stopping ASN-Fingolimod.
- 14.
Symptoms of PRES
Inform patients that the symptoms of posterior reversible encephalopathy syndrome (PRES) may include sudden onset of severe headache, confusion, seizures and vision changes.
- 15.
Risk of tumefactive lesions
Inform patients that a condition with unusually large brain lesions associated with MS relapse have been rarely reported in patients treated with fingolimod (a condition called tumefactive lesions). Advise patients that in case of severe relapse, a MRI scan may be performed to evaluate this condition and a decision to stop treatment can be made on a case by case basis.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
A total of 1703 adult patients on fingolimod capsules (0.5 or 1.25 mg dose) constituted the safety population in the two Phase III studies (D2301 and D2302) for approval in patients with relapsing-remitting multiple sclerosis (see CLINICAL TRIALS). Study D2301 (FREEDOMS) was a 2-year placebo-controlled clinical study involving 1272 multiple sclerosis adult patients treated with fingolimod (854: 425 on fingolimod 0.5 mg, 429 on fingolimod 1.25 mg) or placebo (418).
In this study, the most serious adverse events (AEs) for the 0.5 mg recommended therapeutic dose were infections, macular edema, and bradycardia or atrioventricular blocks on treatment initiation (see WARNINGS AND PRECAUTIONS). The most frequent AEs (incidence ≥10% and more frequent than with placebo) reported with the 0.5 mg dose were headache, influenza, diarrhea, back pain, liver enzyme elevations and cough. The only adverse event that led to more than 1% of patients receiving fingolimod 0.5 mg to stop therapy was serum transaminase elevations, leading to drug discontinuation in 3.8% of patients.
Study D2302 (TRANSFORMS) was a 1-year controlled study using interferon beta-1a as comparator involving 1280 adult patients with multiple sclerosis treated with fingolimod (849: 429 on fingolimod 0.5 mg, 420 on fingolimod 1.25 mg) or interferon beta-1a (431). In Study D2302, the most frequently reported AEs (> 10%), serious AEs and AEs leading to discontinuation were generally similar to those reported in placebo-controlled studies, taking into account the differences in study duration.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Treatment emergent adverse events (AEs) are listed according to MedDRA system organ class.
Table 1 - Treatment emergent AEs occurring in ≥1% of patients in Study D2301, and reported for Fingolimod 0.5 mg at ≥1% higher rate than for placebo.
| Primary system organ class Preferred Term | Placebo N=418 (%) | Fingolimod 0.5mg N=425 (%) |
|---|---|---|
| Infections | 15 (3.6) | 34 (8.0) |
| Influenza viral infections | 41 (9.8) | 55 (12.9) |
| Primary system organ class Preferred Term | Placebo N=418 (%) | Fingolimod 0.5mg N=425 (%) |
|---|---|---|
| Bronchitis | 15 (3.6) | 34 (8.0) |
| Sinusitis | 19 (4.5) | 28 (6.6) |
| Gastroenteritis | 13 (3.1) | 19 (4.5) |
| Pneumonia* | 1 (0.2) | 2 (0.5) |
| Herpes viral infections* | 33 (7.9) | 37 (8.7) |
| Tinea infections | 6 (1.4) | 16 (3.8) |
| Cardiac Disorders | ||
| Bradycardia | 4 (1.0) | 15 (3.5) |
| Nervous system disorders | ||
| Headache | 96 (23.0) | 107 (25.2) |
| Dizziness | 23 (5.5) | 31 (7.3) |
| Paresthesia | 18 (4.3) | 23 (5.4) |
| Migraine | 6 (1.4) | 20 (4.7) |
| Gastrointestinal disorders | ||
| Diarrhea | 31 (7.4) | 50 (11.8) |
| General disorders and administration site conditions | ||
| Asthenia | 5 (1.2) | 11 (2.6) |
| Musculoskeletal and connective tissue disorders | ||
| Back pain | 29 (6.9) | 50 (11.8) |
| Skin and subcutaneous tissue disorders | ||
| Eczema | 8 (1.9) | 14 (3.3) |
| Alopecia | 10 (2.4) | 15 (3.5) |
| Pruritus | 5 (1.2) | 11 (2.6) |
| Investigations | ||
| Alanine transaminase (ALT) increased | 16 (3.8) | 43 (10.1) |
| Gamma-glutamyl transferase (GGT) increased | 4 (1.0) | 22 (5.2) |
| Hepatic enzyme increased | 1 (0.2) | 14 (3.3) |
| Weight decreased | 14 (3.3) | 20 (4.7) |
| Blood triglycerides increased | 5 (1.2) | 11 (2.6) |
| Liver function test abnormal | 1 (0.2) | 6 (1.4) |
| Respiratory, thoracic and mediastinal disorders |
| Primary system organ class Preferred Term | Placebo N=418 (%) | Fingolimod 0.5mg N=425 (%) |
|---|---|---|
| Cough | 34 (8.1) | 43 (10.1) |
| Dyspnea | 19 (4.5) | 34 (8.0) |
| Psychiatric disorders | ||
| Depression | 28 (6.7) | 33 (7.8) |
| Eye disorders | ||
| Eye pain | 6 (1.4) | 11 (2.6) |
| Vision blurred | 6 (1.4) | 15 (3.5) |
| Vascular disorders | ||
| Hypertension | 16 (3.8) | 27 (6.4) |
| Blood and lymphatic system disorders | ||
| Leucopenia | 1 (0.2) | 12 (2.8) |
| Lymphopenia | 2 (0.5) | 15 (3.5) |
| * Plausible relationship to study drug |
Infections
In the two-year multiple sclerosis clinical trial, the overall rate of infections (72%) and serious infections (2%) at the 0.5 mg dose was similar to placebo. However, bronchitis and pneumonia were more common in fingolimod -treated patients (Table 1).
There have been very rare fatal cases of VZV infections in patients taking fingolimod (at the recommended dose or higher doses used in clinical trials). These patients received prolonged concomitant corticosteroid use (more than 5 days) for treatment of multiple sclerosis relapses.
There have been very rare cases of other herpes viral infections with fatal outcome. Some cases of disseminated herpes infections have been reported, including fatal cases, with one case at the
0.5 mg dose (see WARNINGS AND PRECAUTIONS, Herpetic Infections).
Human papilloma virus (HPV) infection, including papilloma, dysplasia, warts and HPV-related cancer, has been reported under treatment with fingolimod capsules in the post-marketing setting (see WARNINGS AND PRECAUTIONS, Human papilloma virus).
Macular Edema
In clinical trials, macular edema occurred in 0.4% of patients treated with the recommended fingolimod dose of 0.5 mg, 1.1% of patients treated with the higher 1.25 mg dose, and in 0.1% of patients that received placebo.
The majority of cases in multiple sclerosis clinical trials occurred within the first 3-4 months of therapy. Some patients presented with blurred vision or decreased visual acuity, but others were asymptomatic and diagnosed on routine ophthalmic examination. Treatment with fingolimod was discontinued in all cases of macular edema. The macular edema generally improved or resolved spontaneously after drug discontinuation. The risk of recurrence after re-challenge has not been evaluated (see WARNINGS AND PRECAUTIONS, Ophthalmologic).
Macular edema incidence is increased in multiple sclerosis patients with a history of uveitis (approximately 20% in those with a history of uveitis vs. 0.6% without a history of uveitis).
Patients with diabetes mellitus were excluded from multiple sclerosis clinical trials. In renal transplant clinical studies where patients with diabetes mellitus were included, the incidence of macular edema was several-fold greater in patients with diabetes compared to non-diabetic patients. In addition, therapy with fingolimod 2.5 mg and 5 mg resulted in a 2-fold increase in the incidence of macular edema in those studies. Multiple sclerosis patients with diabetes mellitus are therefore expected to be at a higher risk for macular edema (see WARNINGS AND PRECAUTIONS, Ophthalmologic).
ECG Findings
Fingolimod was associated with PR interval prolongation, QTc interval prolongation, and decreased heart rate (see WARNINGS AND PRECAUTIONS, Cardiovascular; DRUG INTERACTIONS, Pharmacodynamic Interactions; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Heart rate and rhythm, -Thorough QT Study).
Bradyarrhythmia
Initiation of fingolimod treatment results in a reversible decrease in heart rate that may also be associated with AV conduction delays (see WARNINGS AND PRECAUTIONS, Cardiovascular; DRUG INTERACTIONS, Pharmacodynamic Interactions; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Heart rate and rhythm).
In multiple sclerosis clinical trials the mean maximum decrease in heart rate after taking the first dose was seen within 6 hours post-dose, with a decline in the mean heart rate of 8 beats per minute for fingolimod 0.5 mg at 5 h post-dosing. The placebo-adjusted change in mean hourly heart rate at 6 h post-dosing was approximately 13 beats per minute according to 24 h Holter monitoring. The second dose may result in a slight further decrease. Patients who experienced bradycardia were generally asymptomatic but some patients experienced mild to moderate symptoms, including hypotension, dizziness, fatigue, palpitations, and/or chest pain or chest discomfort, which resolved within the first 24 hours of treatment. Heart rate returned to baseline within 1 month of chronic dosing.
In the multiple sclerosis clinical trial program first-degree AV block (prolonged PR interval on ECG) was detected following drug initiation in 4.7% of patients receiving fingolimod 0.5 mg, in
2.8% of patients receiving intramuscular interferon beta-1a and in 1.5% of patients receiving placebo. Second-degree AV block Mobitz type 1 (Wenckebach) was detected in 0.2% of adult patients on fingolimod 0.5 mg.
Isolated reports of complete AV block during the 6 hour observation period and delayed onset cardiac events, including transient asystole and unexplained death within 24 hours of the first dose, have been reported during post-marketing experience (see ADVERSE REACTIONS, Post- Market Adverse Events). These events were confounded by concomitant and/or pre-existing disease, and the relationship to fingolimod cannot be excluded.
The conduction abnormalities observed both in clinical trials and post-marketing were typically transient, asymptomatic and resolved within 24 hours. Although most patients in clinical trials did not require medical intervention, one patient on the 0.5 mg dose received isoprenaline (isoproterenol) for an asymptomatic 2nd-degree Mobitz I AV block.
Blood pressure
Fingolimod is associated with a decrease of blood pressure after the first dose. Chronic treatment is associated with an increase in blood pressure.
On the first day of treatment in multiple sclerosis clinical trials, fingolimod was associated with a decrease in systolic, diastolic, and mean arterial BP, starting at 1 hour post-dose, reaching its maximal decrease after 4-5 hours. The maximal decrease from pre-dose values in mean arterial BP was 3.5 mmHg (5 hours post-dose) in the fingolimod 0.5 mg group compared to a maximal mean decrease of 1.8 mmHg (4 hours post-dose) in the placebo group (see WARNINGS AND PRECAUTIONS, Cardiovascular; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Blood Pressure). Cases of syncope were also reported after the first dose of fingolimod in the post-marketing setting.
In multiple sclerosis clinical trials fingolimod 0.5 mg was associated with increases of approximately 2 mmHg in systolic pressure, and 1 mmHg in diastolic pressure manifesting after approximately 1 month of treatment initiation. These increases persisted with continued treatment. In controlled studies involving 854 multiple sclerosis patients on fingolimod 0.5 mg and 511 multiple sclerosis patients on placebo, hypertension was reported as an adverse reaction in 5% of patients on fingolimod 0.5 mg and in 3% of patients on placebo.
Vascular events
Rare cases of ischemic stroke and hemorrhagic stroke have been reported in patients treated with fingolimod in clinical trials and in the post-marketing setting. The relationship to fingolimod remains uncertain. In phase III clinical trials, rare cases of peripheral arterial occlusive disease occurred in patients receiving fingolimod at doses of 1.25 mg (2.5 times the recommended dose) and 5.0 mg (10 times the recommended dose).
Neoplasms
There have been cases of cutaneous neoplasms and lymphoma reported in clinical studies and the post-marketing setting (see WARNINGS AND PRECAUTIONS, Neoplasms).
Basal cell carcinoma and other cutaneous neoplasms
In pooled data from the two placebo-controlled Phase III clinical trials, D2301 (FREEDOMS) and D2309 (FREEDOMS II), basal cell carcinoma has been reported in 14/783 (1.8%) patients receiving fingolimod, and in 5/773 (0.6%) patients on placebo.
During Phase III placebo controlled clinical trials there was no difference in the frequency of melanoma in patients treated with fingolimod for up to 2 years, compared to patients receiving placebo. In open label clinical trials and in the post-marketing setting, melanoma has been reported in a small number of patients, who were treated with fingolimod, and who had no apparent risk factors, signs of melanoma at treatment initiation or concurrent medical conditions (see WARNINGS AND PRECAUTIONS, Neoplasm).
Kaposi’s sarcoma has been reported in clinical trials and in the post-marketing setting in patients treated with fingolimod who did not have risk factors commonly associated with Kaposi’s sarcoma.
Lymphoma
Cases of lymphoma have been reported in clinical studies and the post-marketing setting. The reported lymphoma cases were heterogeneous in nature, mainly Non-Hodgkin’s Lymphoma, including B-cell and T-cell lymphomas. Cases of cutaneous T-cell lymphoma (including mycosis fungoides) have been observed in the post-marketing setting.
Respiratory system
Dose-dependent reductions in forced expiratory volume over 1 second (FEV1) and diffusion lung capacity for carbon monoxide (DLCO) were observed in patients treated with fingolimod as early as 1 month after treatment initiation (see WARNINGS AND PRECAUTIONS, Respiratory). At Month 24, the reduction from baseline in the percent of predicted values for FEV1 was 3.1% for fingolimod 0.5 mg and 2.0% for placebo, corresponding to a mean decrease of 150 mL/s and 120 mL/s, respectively. For DLCO, the reductions from baseline in percent of predicted values at Month 24 were 3.8% for fingolimod 0.5 mg and 2.7% for placebo. The changes in FEV1 appear to be reversible after treatment discontinuation, but there is insufficient information to determine the reversibility of the decrease of DLCO after drug discontinuation.
In the 24-month multiple sclerosis placebo-controlled trial, dyspnea was reported in 7.1% of patients receiving fingolimod 0.5 mg and 4.5% of patients receiving placebo. Several patients discontinued fingolimod because of unexplained dyspnea during the extension (uncontrolled) studies.
Seizures
Cases of seizures, including status epilepticus, have been reported with the use of fingolimod in clinical trials and in the post-marketing setting. In clinical trials, the rate of seizures was 0.9% in fingolimod treated patients and 0.3% in placebo treated patients. It is unknown whether these events were related to the effects of multiple sclerosis alone, to fingolimod, or to a combination of both.
Other Adverse Events Observed During Double blind Controlled Clinical Trials in MS
The D2309 study (FREEDOMS II) was a 2-year prospective, double blind study designed to evaluate the efficacy, safety, and tolerability of two doses of fingolimod (1.25 mg and 0.5 mg) compared with placebo in patients with RRMS. This Phase III study was completed after the approval of the fingolimod. The three arms of the study were fingolimod 1.25 mg (n=370); fingolimod 0.5 mg (n=358) and placebo (n=355). The safety data from the study were very consistent with the D2301 study. In this study, the incidence of increased AST adverse events was higher for fingolimod (0.5 mg) than placebo (3.1% vs 1.4%).
Post-Market Adverse Reactions
The following adverse reactions have been reported during post-marketing experience:
Cardiac Disorders: Isolated reports of transient, spontaneously resolving complete AV block have been observed during the six-hour observation period with fingolimod. Isolated delayed- onset events, including transient asystole and unexplained death, have occurred within 24 hours of the first dose of fingolimod. These cases have been confounded by concomitant medications and/or pre-existing disease, but the relationship to fingolimod cannot be excluded.
Infections and Infestations: Hemophagocytic syndrome with fatal outcome has been reported with fingolimod treatment in the context of infection. Hemophagocytic syndrome is a rare condition that has been described in association with infections and a variety of autoimmune disease and cases have been reported in patients with MS.
Cases of infections with opportunistic viral (e.g. VZV, JCV causing PML, HSV), fungal (e.g. cryptococci including cryptococcal meningitis), or bacterial (e.g. atypical mycobacterium) pathogens, have been reported, some of which have been fatal (see WARNINGS AND PRECAUTIONS, Immune).
Immune system disorders: Hypersensitivity reactions, including rash, urticaria and angioedema upon treatment initiation.
Gastrointestinal disorders: nausea
Hematologic: thrombocytopenia
Investigations: Weight decreased
Musculoskeletal and connective tissue disorders: Myalgia, arthralgia
Nervous system disorders: Severe exacerbation of disease after fingolimod discontinuation, posterior reversible encephalopathy syndrome, seizures including status epilepticus (see WARNINGS AND PRECAUTIONS)
Neoplasms, benign, malignant, and unspecified (incl cysts and polyps): melanoma, squamous cell carcinoma, Merkel cell carcinoma, Kaposi’s sarcoma, B-cell lymphoma, T-cell lymphoma, CNS lymphoma, cutaneous T-cell lymphoma (including mycosis fungoides).
Because adverse reactions identified during post-marketing use are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or to establish a causal relationship to drug exposure.
Abnormal Hematologic and Clinical Chemistry Findings
Liver function
Increased hepatic enzymes (mostly ALT elevation) have been reported in multiple sclerosis patients treated with fingolimod. In clinical trials in adults, patients treated with fingolimod experienced an asymptomatic elevation in serum levels of ALT, irrespective of adverse event reporting. Three-fold or greater increases in ALT were seen in 8.5% of patients receiving fingolimod 0.5 mg compared to 1.7% of those on placebo while ≥5-fold elevations were seen in 1.9% and 1.0% of patients, respectively, in the two-year placebo-controlled multiple sclerosis clinical trial. The majority of ALT elevations occurred within 6-9 months of initiating treatment with fingolimod. Findings were similar, but less frequent for AST and GGT.
ALT levels returned to normal after discontinuation of fingolimod within approximately 2 months. In a small number of patients (2 patients on fingolimod 0.5 mg), who experienced liver transaminase elevations of ≥5x ULN and who continued on fingolimod therapy, the ALT levels returned to normal within approximately 5 months (see WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
Cholesterol and Triglycerides
In the 24 month placebo-controlled multiple sclerosis clinical trial D2301, total cholesterol and triglyceride levels were increased during treatment with fingolimod 0.5 mg from Week 2 to Month 24. The incidence of notable high cholesterol levels (> 6.21 mmol/L) was 39.6% for fingolimod 0.5 mg and 31.9% for placebo. The incidence of notable high triglyceride levels (> 3.39 mmol/L) was 13.7% for fingolimod 0.5 mg and 7.5% for placebo.
DRUG INTERACTIONS
Overview
Pharmacodynamic interactions
Anti-neoplastic, immunosuppressive or immune-modulating drugs: Co-administration of anti-neoplastic, immunosuppressive or immune modulating therapies is not recommended due to the risk of additive immune system effects. Caution should also be applied when switching patients from long-acting therapies with immune effects such as natalizumab, teriflunomide or mitoxantrone (see WARNINGS AND PRECAUTIONS, Immune).
Co-administration of a short course of corticosteroids (up to five days as per study protocol) to treat relapses did not increase the overall rate of infection in patients treated with fingolimod in the Phase III clinical trials, compared to placebo (see WARNINGS and PRECAUTIONS and ADVERSE REACTIONS). Patients should be reminded of the potential for increased risk of infection due to the risk of additive immune system effects of corticosteroids.
Heart rate lowering drugs: Fingolimod treatment results in PR interval prolongation during the first week and heart rate decrease during the first month of treatment. Due to potential additive effects on heart rate or cardiac conduction, ASN-Fingolimod should not be used concomitantly with heart rate lowering drugs (e.g. antiarrhythmics, beta blockers, calcium channel blockers) (see WARNINGS AND PRECAUTIONS, Cardiovascular; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Heart rate and rhythm).
Fingolimod has been studied in combination with atenolol or diltiazem. When a single dose of fingolimod 5 mg/day was used with atenolol 50 mg/day (steady state) in an interaction study in healthy volunteers, there was an additional 15% reduction of heart rate at fingolimod treatment initiation, an effect not seen with diltiazem 240 mg/day (steady state).
ASN-Fingolimod should not be initiated in patients receiving beta-blockers, heart-rate-lowering calcium channel blockers (such as verapamil or diltiazem), or other substances that may decrease heart rate (e.g. digoxin, cholinesterase inhibitors, or pilocarpine) because of the potential additive effects on heart rate. If treatment with ASN-Fingolimod is considered necessary, advice from a cardiologist should be sought regarding the switch to a non heart-rate lowering drug or for appropriate monitoring (e.g., at least overnight monitoring) during treatment initiation, if the heart-rate-lowering drugs cannot be discontinued (see WARNINGS AND PRECAUTIONS, Cardiovascular).
QTc prolonging drugs: Fingolimod may result in QTc prolongation during the first month of treatment (See WARNINGS AND PRECAUTIONS, Cardiovascular; ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics-Thorough QT Study). Fingolimod capsules have not been studied in patients treated with drugs that prolong the QT interval.
Class Ia antiarrhythmics (e.g., quinidine, disopyramide) and Class III antiarrhythmics (e.g., amiodarone, sotalol) may prolong the QTc interval and have been associated with cases of torsades de pointes in patients with bradycardia and these drugs were excluded from use in multiple sclerosis clinical trials. Since initiation of fingolimod treatment results in both a decreased heart rate and a prolongation of QTc interval, ASN-Fingolimod should not be used concomitantly with Class Ia or Class III drugs (see WARNINGS AND PRECAUTIONS, Cardiovascular-Bradyarrhythmia).
The initiation of treatment with ASN-Fingolimod in a patient taking other types of QTc prolonging drugs should be avoided. If a decision is made to undertake treatment such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring, which should be at least overnight.
In addition to the Class Ia and Class III antiarrhythmic drugs, other drugs that have been associated with QTc interval prolongation and/or torsade de pointes include, but are not limited to, the examples found below. Chemical/ pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QTc prolongation and/or torsade de pointes:
Class 1C antiarrhythmics (e.g., flecainide, propafenone); antipsychotics (e.g., chlorpromazine, haloperidol); antidepressants (e.g., fluoxetine, tricyclic/tetracyclic antidepressants e.g., amitriptyline, imipramine, maprotiline); opioids (e.g., methadone); macrolide antibiotics and analogues (e.g., erythromycin, clarithromycin, tacrolimus); quinolone antibiotics (e.g., ciprofloxacin); antimalarials (e.g., quinine, chloroquine); azole antifungals (e.g., ketoconazole); domperidone; 5-HT3 receptor antagonists (e.g., ondansetron); tyrosine kinase inhibitors (e.g., sunitinib); histone deacetylase inhibitors (e.g., vorinostat); beta-2 adrenoceptor agonists (e.g., salmeterol).
Current information sources should be consulted for newly approved drugs that prolong the QT/QTc interval as well as for older drugs for which this effect has recently been established.
Vaccines: During and for up to 2 months after treatment with ASN-Fingolimod vaccination may be less effective. The use of live attenuated vaccines may carry the risk of infection and should therefore also be avoided during ASN-Fingolimod treatment and for up to 2 months after treatment with ASN-Fingolimod (see WARNINGS AND PRECAUTIONS, Immune - Vaccination).
Pharmacokinetic interactions
Fingolimod is primarily cleared via human cytochrome P450 4F2 (CYP4F2) and possibly other CYP4F isoenzymes. In vitro studies in hepatocytes indicated that CYP3A4 may contribute to fingolimod metabolism in the case of strong induction of CYP3A4.
Potential of fingolimod and fingolimod-phosphate to inhibit the metabolism of comedications
In vitro inhibition studies using pooled human liver microsomes and specific metabolic probe substrates demonstrated that fingolimod and fingolimod-phosphate have little or no capacity to inhibit the activity of CYP enzymes (CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP2E1, CYP3A4/5, or CYP4A9/11 (fingolimod only)). Therefore, fingolimod and fingolimod-phosphate are unlikely to reduce the clearance of drugs that are mainly cleared through metabolism by the major CYP isoenzymes.
Potential of fingolimod and fingolimod-phosphate to induce its own and/or the metabolism of co-medications
Fingolimod was examined for its potential to induce human CYP3A4, CYP1A2, CYP4F2, and ABCB1 (P-gp or P-glycoprotein) mRNA and CYP3A, CYP1A2, CYP2B6, CYP2C8, CYP2C9,
CYP2C19, and CYP4F2 activity in primary human hepatocytes. Fingolimod did not induce mRNA or activity of the different CYP enzymes and ABCB1 with respect to the vehicle control. Therefore, no clinically relevant induction of the tested CYP enzymes or ABCB1 (P-gp) by fingolimod is expected at therapeutic concentrations. In vitro experiments did not provide an indication of CYP induction by fingolimod-phosphate.
Potential of fingolimod and fingolimod-phosphate to inhibit the active transport of co- medications
Based on in vitro data, fingolimod as well as fingolimod-phosphate are not expected to inhibit the uptake of co-medications and/or biologics transported by the organic anion transporting polypeptides 1B1 and 1B3 (OATP1B1, OATP1B3) or the sodium taurocholate co-transporting polypeptide (NTCP). Similarly, they are not expected to inhibit the efflux of co-medications and/or biologics transported by the breast cancer resistance protein (BCRP), the bile salt export pump (BSEP), the multidrug resistance-associated protein 2 (MRP2) or P-glycoprotein (P-gp) at therapeutic concentrations.
Drug-Drug Interactions
Oral contraceptives
In an open label two-period study, healthy female volunteers (n=31) on a steady regimen of oral contraceptive (ethinylestradiol and levonorgestrel) received the oral contraceptive alone for 14 days, followed by co-administration of the oral contraceptive and fingolimod 0.5 mg/day for an additional 14 days. The steady state co-administration of fingolimod and the oral contraceptive did not elicit any change in oral contraceptive exposure. Fingolimod and fingolimod-phosphate exposure were consistent with those from previous studies.
No interaction studies have been performed with oral contraceptives containing other progestogens, however an effect of fingolimod on their exposure is not expected.
Cyclosporine
The pharmacokinetics of single-dose fingolimod were not altered during co-administration with cyclosporine at steady-state, nor were cyclosporine (CYP3A4 substrate) steady-state pharmacokinetics altered by single-dose, or multi-dose (28 days) fingolimod administration. These data suggest that fingolimod is not likely to reduce or increase the clearance of drugs mainly cleared by CYP3A4 and that inhibition of CYP3A4 is unlikely to reduce the clearance of fingolimod. Potent inhibition of transporters P-gp, MRP2 and OATP1B1 does not influence fingolimod disposition.
Ketoconazole
In an open-label, two-period crossover study, healthy volunteers (N=22) received a single dose of 5 mg fingolimod on Day 1 of the first period and ketoconazole 200 mg twice daily for 9 days during the second period, with a single 5 mg dose of fingolimod administered on the fourth day of ketoconazole treatment. The co-administration of ketoconazole 200 mg twice daily at steady- state and a single dose of fingolimod 5 mg led to a 1.7-fold increase in the AUC of fingolimod and fingolimod-phosphate by inhibition of CYP4F2. This study did not evaluate the effect of chronic co-administration of ketoconazole, a potent inhibitor of CYP3A and CYP4F2, on fingolimod pharmacokinetics. Therefore, caution should be exercised during chronic co- administration of ASN-Fingolimod and systemic ketoconazole and patients should be closely monitored as the risk of adverse events may be increased.
Isoproterenol and atropine
Single-dose fingolimod and fingolimod-phosphate exposure was not altered by co-administered isoproterenol, or atropine.
Carbamazepine
The co-administration of carbamazepine 600 mg twice daily at steady-state and a single dose of fingolimod 2 mg decreased the AUC of fingolimod and fingolimod-phosphate by approximately 40%. The clinical relevance of this decrease is unknown; however, the co-administration of carbamazepine may decrease the efficacy of fingolimod treatment.
Drug-Laboratory Interactions
Since fingolimod reduces blood lymphocyte counts via re-distribution in secondary lymphoid organs, peripheral blood lymphocyte counts cannot be utilized to evaluate the lymphocyte subset status of a patient treated with ASN-Fingolimod.
Laboratory tests requiring the use of circulating mononuclear cells require larger blood volumes due to reduction in the number of circulating lymphocytes.
DOSAGE AND ADMINISTRATION
Dosing Considerations
See WARNINGS AND PRECAUTIONS, Cardiovascular for complete information on patients with certain cardiovascular conditions in which ASN-Fingolimod should not be used or which may require additional monitoring.
Conditions when ASN-Fingolimod should not be used
- ASN-Fingolimod should not be initiated in patients on concurrent therapy with beta-blockers, with heart-rate lowering calcium channel blockers or with other substances that may decrease heart rate. If treatment with ASN-Fingolimod is considered necessary, advice from a cardiologist should be sought regarding a switch to drugs that do not lower heart rate or for appropriate monitoring during treatment initiation, if the heart-rate-lowering drugs cannot be discontinued (see WARNINGS AND PRECAUTIONS, Cardiovascular-Bradyarrhythmia; DRUG INTERACTIONS-Heart rate lowering drugs).
- The use of ASN-Fingolimod with drugs that prolong the QT interval should be avoided. If a decision is made to undertake treatment such patients should be evaluated by a cardiologist prior to initiation of treatment, to assess suitability and to determine the most appropriate monitoring, which should be at least overnight (see WARNINGS AND PRECAUTIONS, Cardiovascular-QTc prolongation; DRUG INTERACTIONS-QTc prolonging drugs).
See WARNINGS AND PRECAUTIONS, Cardiovascular-Bradyarrhythmia for other conditions when ASN-Fingolimod should not be used.
First dose monitoring of fingolimod
- For all patients, obtain an ECG and measure blood pressure prior to dosing and 6-hours after the first dose.
- Monitor all patients for signs and symptoms of bradyarrhythmia, with hourly pulse and blood pressure measurements, for at least 6 hours after the first dose.
- If symptoms of bradyarrhythmia or AV block occur, initiate appropriate management, with continued monitoring (e.g., continuous ECG) until the symptoms have resolved (see WARNINGS AND PRECAUTIONS, Cardiovascular, Bradyarrhythmia).
The same precautions as for the first dose should be taken when patients are switched from the 0.25 mg to the 0.5 mg daily dose.
See WARNINGS AND PRECAUTIONS, Cardiovascular-Bradyarrhythmia for additional recommendations for extended monitoring.
- Patients should be advised that the ability to drive an automobile or operate dangerous equipment may be impaired during the first day of treatment.
- Re-initiation of fingolimod after a treatment interruption of more than 2 weeks after the first month of treatment may produce the same effect on heart rate as the initial dose. Patients should be monitored as for the first dose. Within the first 2 weeks of treatment, first-dose procedures are recommended after an interruption of one day or more. During week 3 and 4 of treatment, first dose procedures are recommended after a treatment interruption of more than 7 days (see WARNINGS AND PRECAUTIONS, Cardiovascular-Re-initiation of therapy following discontinuation).
Dosing in special populations
- Renal impairment: ASN-Fingolimod should be used with caution in patients with severe renal impairment (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
Hepatic impairment: ASN-Fingolimod is contraindicated in patients with severe hepatic
- impairment (Child-Pugh class C) (see CONTRAINDICATIONS). Although dose adjustments are not needed in patients with mild and moderate hepatic impairment, caution should be exercised when initiating ASN-Fingolimod treatment in these patients (ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions; WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic-Liver Function).
- Pediatric patients: ASN-Fingolimod is not indicated for use in pediatric patients (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
- Geriatric patients: ASN-Fingolimod should be used with caution in patients aged 65 years and over due to the greater frequency of reduced hepatic, renal, immune, pulmonary and cardiovascular function, other concomitant diseases and concomitant drug therapy (see CONTRAINDICATIONS; WARNINGS AND PRECAUTIONS, Special Populations; ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
- Ethnicity: No ASN-Fingolimod dose adjustments are needed based on ethnic origin (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
- Gender: No ASN-Fingolimod dose adjustments are needed based on gender (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics-Special Populations and Conditions).
- Diabetic patients: ASN-Fingolimod should be used with caution in patients with diabetes mellitus due to a potential increased risk of macular edema (see ADVERSE REACTIONS, Macular Edema). Multiple sclerosis patients with concomitant diabetes mellitus were excluded from the clinical trials with fingolimod.
Recommended Dose and Dosage Adjustment
In adults, the recommended dose of ASN-Fingolimod is 0.5 mg once daily.
Patients already on beta interferon or glatiramer acetate therapy can switch directly to ASN-Fingolimod if they do not display signs of treatment-related abnormalities such as cytopenia. Caution is advised when switching patients from natalizumab or teriflunomide to ASN-Fingolimod. For recommendations related to switching patients from other disease modifying therapies to ASN-Fingolimod, see WARNINGS AND PRECAUTIONS: Immune - Prior treatment with immunosuppressive or immune-modulating therapies.
Missed Dose
If a dose is missed, treatment should be continued with the next dose as planned.
If the treatment is interrupted for one day or more during the first two weeks of treatment, first dose procedures are recommended upon re-initiation (see WARNINGS AND PRECAUTIONS, Cardiovascular – Re-initiation Therapy Following discontinuation).
If fingolimod therapy is discontinued for more than 2 weeks, after the first month of treatment, the effects on heart rate and AV conduction may recur on reintroduction of fingolimod treatment and the same precautions as for the first dose should apply (i.e., monitor for at least 6 hours after the first dose). Within the first 2 weeks of treatment, first-dose procedures are recommended after an interruption of one day or more. During weeks 3 and 4 of treatment, first dose procedures are recommended after a treatment interruption of more than 7 days.
Administration
ASN-Fingolimod is taken orally, with or without food.
OVERDOSAGE
| For management of a suspected drug overdose, contact your regional poison control centre. |
Single doses of fingolimod up to 40 mg (80-fold the recommended dose of 0.5mg) were well tolerated in healthy adult volunteers. Fingolimod doses of 5 mg to 40 mg were associated with a mild to moderate, dose dependent decrease in FEV1. At 40 mg, 5 of 6 subjects reported mild chest tightness or discomfort which was clinically consistent with small airway reactivity.
Fingolimod can induce bradycardia. The decline in heart rate usually starts within one hour of the first dose, and is maximal within 6 hours. There have been reports of slow atrioventricular conduction with isolated reports of transient, spontaneously resolving complete AV block (see WARNINGS AND PRECAUTIONS-Cardiovascular; and ADVERSE DRUG REACTIONS-
Bradyarrhythmia, -Post Market Adverse Events).
In case of ASN-Fingolimod overdosage, observe patients overnight with continuous ECG monitoring in a medical facility and obtain regular measurements of pulse rate and blood pressure (see DOSAGE AND ADMINISTRATION-Dosing Considerations; and WARNINGS AND PRECAUTIONS-Cardiovascular).
Neither dialysis nor plasma exchange results in removal of fingolimod from the body.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Fingolimod is metabolized by sphingosine kinase to the active metabolite fingolimod-phosphate.
Fingolimod-phosphate, binds with high affinity to sphingosine 1-phosphate (S1P) receptors 1, 3, 4, and 5. Fingolimod-phosphate binding to S1P receptors on lymphocytes induces S1P receptor down-regulation on lymphocytes, and blocks the capacity of lymphocytes to egress from lymph nodes, reducing the number of lymphocytes in peripheral blood. The mechanism by which fingolimod exerts therapeutic effects in multiple sclerosis is not known, but may involve reduction of lymphocyte migration into the central nervous system.
Pharmacodynamics
Immune system
Effects on immune cell numbers in the blood. In a study in which 12 subjects were treated with fingolimod 0.5 mg/day for 28 days, the mean lymphocyte count was decreased to approximately 70% of baseline within 4 hours after the first dose and approximately 50% within 8 hours. With continued daily dosing, the lymphocyte count continued to decrease over a 2-week period, reaching a nadir count of approximately 500 cells/μL or approximately 30% of baseline. Low lymphocyte counts are maintained with chronic daily dosing.
In the 2-year placebo-controlled multiple sclerosis clinical trial in which 425 patients were treated with fingolimod 0.5 mg and 418 patients received placebo, 18% of patients on 0.5 mg fingolimod reached a nadir below 200 cells/μL on at least one occasion. Approximately 4% of patients on 0.5 mg fingolimod had lymphocyte counts below 200 cells/μL on two or more consecutive tests separated by approximately 3 months, and for the majority of these patients’ lymphocyte counts remained at this level for at least 180 days. Treatment was interrupted when patients had confirmed lymphocyte counts below 200 cells/μL and lymphocyte counts were monitored frequently until levels returned to 600 cells/μL.
Peripheral lymphocyte count increases are evident within days of stopping fingolimod treatment. Because elimination of fingolimod after discontinuation of fingolimod may take up to 2 months (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics), recovery of peripheral lymphocyte counts to baseline values is gradual. For patients in multiple sclerosis clinical trials who had lymphocyte count results available both at the end of treatment and during the 3-month interval following discontinuation of treatment, lymphocyte counts returned to normal values within 3 months of discontinuing treatment. Delayed recovery, beyond 3 months, of lymphocyte counts was uncommon and showed a potential correlation with higher doses of fingolimod, the occurrence of lymphocyte counts < 0.2 x 10⁹/L while on treatment, and longer duration of exposure to fingolimod.
Chronic fingolimod dosing leads to a mild decrease in the neutrophil count to approximately 80% of baseline. Monocytes are unaffected by fingolimod.
Effect on antibody response. Immunologic responses are decreased during treatment with fingolimod 0.5 mg. The immunogenicity of keyhole limpet Hemocyanin (KLH) and pneumococcal polysaccharide vaccine (PPV-23) immunization were assessed by IgM and IgG titers in a steady-state, randomized, placebo-controlled study in healthy volunteers. Compared to placebo, antigen-specific IgM titers were decreased by 91% and 25% in response to KLH and PPV, respectively, in subjects on fingolimod 0.5 mg. Similarly, IgG titers were decreased by 45% and 50%, in response to KLH and PPV, respectively, in subjects on fingolimod 0.5 mg daily compared to placebo. The responder rate for fingolimod 0.5 mg as measured by the number of subjects with a >4-fold increase in KLH IgG was comparable to placebo and 25% lower for PPV-23 IgG, while the number of subjects with a >4 fold increase in KLH and PPV-23 IgM was 75% and 40% lower, respectively, compared to placebo. The capacity to mount a skin delayed- type hypersensitivity reaction to Candida and tetanus toxoid was decreased by approximately 30% in subjects on fingolimod 0.5 mg daily, compared to placebo. Immunologic responses were further decreased with fingolimod 1.25 mg (a dose higher than recommended in multiple sclerosis).
In the second study, the immunogenicity of Northern hemisphere seasonal influenza and tetanus toxoid vaccination was assessed in a 12-week steady-state, randomized, placebo-controlled study of fingolimod 0.5 mg in adult multiple sclerosis patients (n = 136). The responder rate 3 weeks after vaccination, defined as seroconversion or a ≥ 4-fold increase in antibody directed against at least 1 of the 3 influenza strains, was 54% for fingolimod 0.5 mg and 85% in the placebo group. The responder rate 3 weeks after vaccination, defined as seroconversion or a ≥ 4-fold increase in antibody directed against tetanus toxoid was 40% for fingolimod 0.5 mg and 61% in the placebo group.
Heart rate and rhythm
Fingolimod causes a reversible prolongation of PR interval and reduction in heart rate upon treatment initiation (see ADVERSE REACTIONS). The maximum decline in heart rate is seen in the first 6 hours post dose, with 70% of the negative chronotropic effect achieved on the first day. Heart rate progressively returns to baseline values within 1 month of chronic treatment.
Autonomic responses of the heart, including diurnal variation of heart rate and response to exercise are not affected by fingolimod treatment.
With initiation of fingolimod treatment there is an increase in atrial premature contractions, but there is no increased rate of atrial fibrillation/flutter, ventricular arrhythmias or ectopy. Fingolimod treatment is not associated with a decrease in cardiac output.
The decrease in heart rate induced by fingolimod can be reversed by atropine, isoproterenol (isoprenaline) or salmeterol.
Thorough QT Study
In a placebo-controlled, double-blind, parallel group study, healthy volunteers were randomized to receive placebo (N=55), fingolimod 1.25 mg (N=53), or fingolimod 2.5 mg (N=61) for 7 days. A loading dose procedure was used to enable steady-state to be reached more quickly. The therapeutic 0.5 mg dose was not studied. Serial ECG recordings were performed for 12 h at baseline and on day 7. Fingolimod was associated with statistically significant QTc prolongation at all time points on day 7, with a maximum effect of 10.9 msec (90% CI 7.88, 13.91) at 6 h post- dosing in the fingolimod 1.25 mg group and 11.1 ms (90% CI 7.56, 14.62) at 6 h post-dosing in the fingolimod 2.5 mg group.
Blood Pressure
Acute dosing with fingolimod resulted in statistically significant decreases in standing systolic and diastolic blood pressure from 2-14 h on Day 1 dosing. The maximum decrease in standing systolic and diastolic blood pressure was -9.5 and -7.6 mmHg respectively at 6 h post-dosing in the fingolimod 1.25 mg treatment group. The therapeutic 0.5 mg dose was not studied. Chronic dosing led to statistically significant increases in systolic and diastolic blood pressure on day 28. (see WARNINGS AND PRECAUTIONS, Cardiovascular; ADVERSE REACTIONS, Blood Pressure).
Pulmonary function
Single doses of fingolimod ≥5 mg (10-fold the recommended dose) are associated with a dose- dependent increase in airway resistance. In a 14-day study of 0.5, 1.25, or 5 mg/day, fingolimod was not associated with impaired oxygenation or oxygen desaturation with exercise or an increase in airway responsiveness to methacholine. Subjects on fingolimod treatment had a normal bronchodilator response to inhaled beta-agonists.
In a placebo-controlled study of subjects with moderate asthma but without multiple sclerosis given fingolimod at doses 0.5mg, 1.25 mg and 2.5 mg or placebo for 10 days (n=9 subjects/group), a significant 10% reduction in mean time-matched, baseline-corrected AUEC FEV1 for the period of 0 to 6 hours after dosing on Day 10 was observed in patients receiving fingolimod 1.25 mg (2.5-times the recommended dose). Changes in FEV1 in the fingolimod 0.5mg and 2.5mg dose groups were, however, not statistically different from those observed in the placebo group. Fingolimod 1.25 mg however was associated with a 5-fold increase in the use of rescue short acting beta-agonists. There was a 2-fold increase (not statistically significant) in the use of rescue short-acting agonists in the fingolimod 0.5 mg group.
Pharmacokinetics
Absorption: The pharmacokinetic parameters of fingolimod 0.5 mg after a single dose and at steady-state are displayed in the table below.
| Fingolimod | Fingolimod-P | ||||||||||||
Single dose | Steady- state | Single dose | Steady- state | ||||||||||
| Tmax, h | 12 | 12 | 6 | 6 | |||||||||
Cmax, ng/mL | 0.42 | 3.66 | 0.45 | 1.81 | |||||||||
AUC0-24h, ng.h/mL | 7.84 | 76.1 | 6.1 | 33.1 | |||||||||
Values are mean, except Tmax (median)
Fingolimod absorption is slow (Tmax of 12-16 hours) and extensive (≥85%, based on the amount of radioactivity excreted in urine and the amount of metabolites in feces extrapolated to infinity). The apparent absolute oral bioavailability is 93%.
Food intake does not alter Cmax or exposure (AUC) of fingolimod or fingolimod-phosphate. The time to reach maximum drug concentration in blood plasma (Tmax) is increased when fingolimod is taken with food. ASN-Fingolimod may be taken without regard to meals (see DOSAGE AND ADMINISTRATION).
Steady-state blood concentrations are reached within 1 to 2 months of once-daily administration, and steady-state levels are approximately 10-fold greater than with the initial dose.
Distribution: Fingolimod highly distributes in red blood cells, with the fraction in blood cells of 86%. Fingolimod-phosphate has a smaller uptake in blood cells of <17%. Fingolimod and fingolimod-phosphate are highly protein bound (>99.7%). Fingolimod and fingolimod-phosphate protein binding is not altered by renal or hepatic impairment.
Fingolimod is extensively distributed to body tissues with a volume of distribution of about 1200±260 L.
Metabolism: The biotransformation of fingolimod in humans occurs by three main pathways; by reversible stereoselective phosphorylation to the pharmacologically active (S)-enantiomer of fingolimod-phosphate, by oxidative biotransformation catalyzed mainly by CYP4F2 and possibly other CYP4F isoenzymes and subsequent fatty acid-like degradation to inactive metabolites, and by formation of pharmacologically inactive non-polar ceramide analogs of fingolimod.
Following single oral administration of [14C] fingolimod, the major fingolimod-related components in blood, as judged from their contribution to the AUC up to 816 hours post-dose of total radio-labeled components, are fingolimod itself (23.3%), fingolimod-phosphate (10.3%), and inactive metabolites (M3 carboxylic acid metabolite (8.3%), M29 ceramide metabolite (8.9%) and M30 ceramide metabolite (7.3%)).
Excretion: Fingolimod blood clearance is 6.3±2.3 L/h, and the average apparent terminal half- life (t1/2) is 6-9 days. Blood levels of fingolimod-phosphate decline in parallel with fingolimod in the terminal phase yielding similar half-life for both.
After oral administration, about 81% of the dose is slowly excreted in the urine as inactive metabolites. Fingolimod and fingolimod-phosphate are not excreted intact in urine but are the major components in the feces with amounts representing less than 2.5% of the dose each. After 34 days, the recovery of the administered dose is 89%.
Special Populations and Conditions
Pediatrics: ASN-Fingolimod is not indicated for use in pediatric patients.
Geriatrics: Clinical studies of fingolimod did not include sufficient numbers of patients aged 65 years and over to determine whether the safety and efficacy of fingolimod differs in elderly patients compared to younger patients. Due to the greater frequency of reduced hepatic, renal, immune, pulmonary and cardiovascular function, other concomitant diseases and concomitant drug therapy, treatment with fingolimod merits caution and may necessitate additional or more frequent monitoring in geriatric patients.
Gender: Gender has no influence on fingolimod and fingolimod-phosphate pharmacokinetics.
Race: The effects of ethnic origin on fingolimod and fingolimod phosphate pharmacokinetics are not of clinical relevance.
Hepatic Insufficiency: The pharmacokinetics of single-dose fingolimod (1 or 5 mg), when assessed in subjects with mild, moderate or severe hepatic impairments (Child-Pugh class A, B, and C), showed no change on fingolimod Cmax, but an increase in AUC by 12%, 44% and 103%, respectively. The apparent elimination half-life is unchanged in mild hepatic impairment but is prolonged by 49-50% in moderate and severe hepatic impairment. The rate of lymphocyte count recovery was approximately 4-fold slower in the subjects with severe hepatic impairment compared to subjects with normal hepatic function. ASN-Fingolimod is contraindicated in patients with severe hepatic impairment (Child-Pugh class C) (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, Special Populations). ASN-Fingolimod should be used with caution in patients with mild and moderate hepatic impairment (Child-Pugh classes A and B). It is not known if patients with hepatic impairment are at increased risk of developing elevated liver function tests, more severe liver injury or other adverse events during treatment with fingolimod.
Renal Insufficiency: Severe renal impairment increases fingolimod Cmax and AUC by 32% and 43%, respectively, and fingolimod-phosphate Cmax and AUC by 25% and 14%, respectively. The apparent elimination half-life is unchanged for both analytes. Exposure to fingolimod metabolites was markedly increased, as shown by a 14-fold increase in AUC for the metabolite M3. The clinical significance of such increase in exposure is not known because the toxicity of this metabolite has not been fully characterized.
Caution is recommended when using ASN-Fingolimod in patients with severe renal impairment (see WARNINGS AND PRECAUTIONS, Special Populations).
The pharmacokinetics of fingolimod and its metabolites in subjects with mild or moderate renal impairment have not been evaluated.
STORAGE AND STABILITY
Store at 15 - 25°C; protect from moisture.
ASN-Fingolimod (fingolimod hydrochloride) must be kept out of the reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
ASN-Fingolimod (fingolimod hydrochloride) is supplied as hard capsules containing 0.5 mg fingolimod (as hydrochloride).
The 0.5 mg capsules have a white opaque body with two radial bands imprinted with yellow ink and a bright yellow opaque cap imprinted with “FIG 0.5 mg” in blank ink. Available in blister packs of 7, 10 and 14 capsules.
0.5 mg hard capsules non-medicinal ingredients: dibasic calcium phosphate, magnesium stearate; capsule shell contains: gelatin, titanium dioxide, iron oxide yellow, edible imprinting ink.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Common name: Fingolimod hydrochloride
Chemical name: 2-amino-2-[2-(4-octylphenyl)ethyl]propane-1,3-diol hydrochloride Molecular formula and molecular mass: C19H33NO2 · HCl
343.9 g/mol
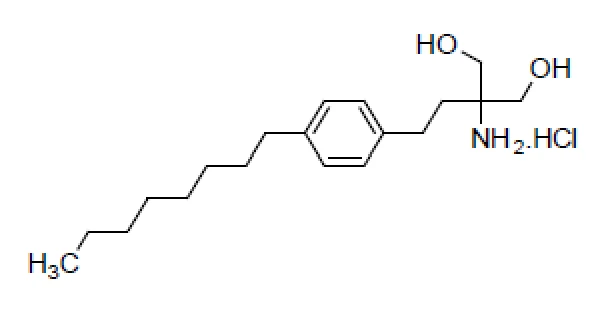
Structural formula:
Physicochemical properties: Description: White to practically white powder
Solubility: Freely soluble in water and ethanol (96%), practically insoluble in heptane.
pH value: pH of 1% w/v solution in water is between 3.0 and 6.0.
CLINICAL TRIALS
Comparative Bioavailability Study
A randomized, double blind, balanced, single dose, two-treatment, two-sequence, two-period, crossover oral bioequivalence study of ASN-Fingolimod 0.5 mg capsules (Ascend Laboratories Ltd.) and GILENYA® 0.5 mg capsules (Novartis Pharmaceutical Industries Ltd.), administered as a single 1 x 0.5 mg dose, was conducted in healthy, adult male subjects under fasting conditions. The results from 30 subjects who completed the study are summarized in the following table:
Fingolimod (1 × 0.5mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test* | Reference† | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-72 (ng.hr/ mL) | 28.78 29.28 (17.71) | 28.45 28.86 (16.17) | 101.14 | 96.34 - 106.19 |
Cmax (ng/ mL) | 0.53 0.53 (15.66) | 0.51 0.51 (15.38) | 103.48 | 99.85 - 107.25 |
Tmax§ (h) | 14.50 (9.00 – 34.00) | 14.00 (8.20 – 34.00) | ||
T½€ (h) | 100.29 (38.07) | 99.34 (41.49) | ||
* ASN-Fingolimod 0.5 mg capsules (Ascend Laboratories Ltd.)
† Gilenya (Fingolimod) capsules 0.5 mg Manufactured by Novartis Pharmaceuticals Canada Inc. and purchased in Canada
§ Expressed as the median (range)
€ Expressed as the arithmetic mean (CV%) only
Study demographics and trial design
Table 2 –Summary of adult patient demographics for clinical trials in RRMS
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| Study D2301 (FREEDOMS) | Randomized, double-blind, placebo- controlled study. | Fingolimod 0.5 mg or 1.25 mg, or placebo, once- daily (oral). 2-year study. | Fingolimod 0.5 mg: n=425 Fingolimod 1.25 mg: n=429 Placebo: n=418 | 37.1 (17-55 years) | Male: 30.1 % Female: 69.9 % |
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| Study D2302 (TRANSFORMS) | Fingolimod 0.5 mg or 1.25 mg, once-daily (oral), or Avonex 30μg, once-weekly (IM). 1-year study. | Fingolimod 0.5 mg: n=429 Fingolimod 1.25 mg: n=420 Avonex: n=431 | 36.2 (18-55 years) | Male: 32.7 % Female: 67.3 % |
The efficacy of fingolimod has been demonstrated in two studies evaluating once daily doses of fingolimod 0.5 mg and 1.25 mg in adult patients with relapsing-remitting multiple sclerosis. Both studies included patients who had experienced at least 2 clinical relapses during the 2 years prior to randomization or at least 1 clinical relapse during the 1 year prior to randomization, and had an Expanded Disability Status Scale (EDSS) score between 0 to 5.5.
Study D2301 (FREEDOMS)
The FREEDOMS study was a 2-year randomized, double-blind, placebo-controlled Phase III study in patients with relapsing-remitting multiple sclerosis who had not received any interferon beta or glatiramer acetate for at least the previous 3 months and had not received any natalizumab for at least the previous 6 months. Neurological evaluations were performed at Screening, every 3 months and at the time of suspected relapse. MRI evaluations were performed at Screening, month 6, month 12 and month 24. The primary endpoint was the annualized relapse rate (ARR).
Median age was 37 years, median disease duration was 6.7 years and median EDSS score at baseline was 2.0. Approximately 40% of patients had received treatment with other disease modifying therapies prior to entering the study, with interferon-beta being the most commonly used prior treatment (used by 29% of all patients). Patients were randomized to receive fingolimod 0.5 mg (n=425) or fingolimod 1.25 mg (n=429), or placebo (n=418) for up to 24 months. Median time on study drug was 717 days on 0.5 mg, 715 days on 1.25 mg and 718.5 days on placebo.
The primary endpoint, the annualized relapse rate was significantly lower in patients treated with fingolimod than in patients who received placebo, with a relative reduction in relapse of 54% for patients treated with fingolimod 0.5 mg. The key secondary endpoint was the time to 3-month confirmed disability progression, as measured by a 1-point increase from baseline in EDSS (0.5 point increase for patients with baseline EDSS of 5.5) sustained for 3 months. Time to onset of 3- month sustained disability progression was significantly delayed with fingolimod treatment compared to placebo. The 1.25 mg dose did not provide additional benefit over the 0.5 mg dose. Results for the Intent to Treat (ITT) analysis of primary and key secondary endpoints of the FREEDOMS study are shown in Table 3 and Figure 1.
Table 4. FREEDOMS study results
| Fingolimod 0.5 mg N=425 | Placebo N=418 | p-value | |||||||
Primary endpoint Annualized relapse rate† | 0.18 | 0.40 | <0.001 | ||||||
Key secondary endpoint Kaplan-Meier estimate of percentage (SE) of patients free of 3-month confirmed disability progression at Month 24 | 82.3 (1.89) | 75.9 (2.17) | 0.026 | ||||||
| Hazard ratio of disability progression (95% CI) | 0.70 (0.52, 0.96) | 0.024 | |||||||
† Based on confirmed relapses. Relapse was defined as neurologic symptoms together with an increase > 0.5 in the total EDSS score, or an increase of 1 point in each of two EDSS functional system scores, or an increase of two points in one EDSS functional system score (excluding bowel-bladder or cerebral functional systems). P-value determined by negative binomial regression adjusting for treatment, pooled country, number of relapses in previous 2 years and baseline EDSS.
Figure 1 Time to 3-month confirmed disability progression – Study D2301 (ITT population)
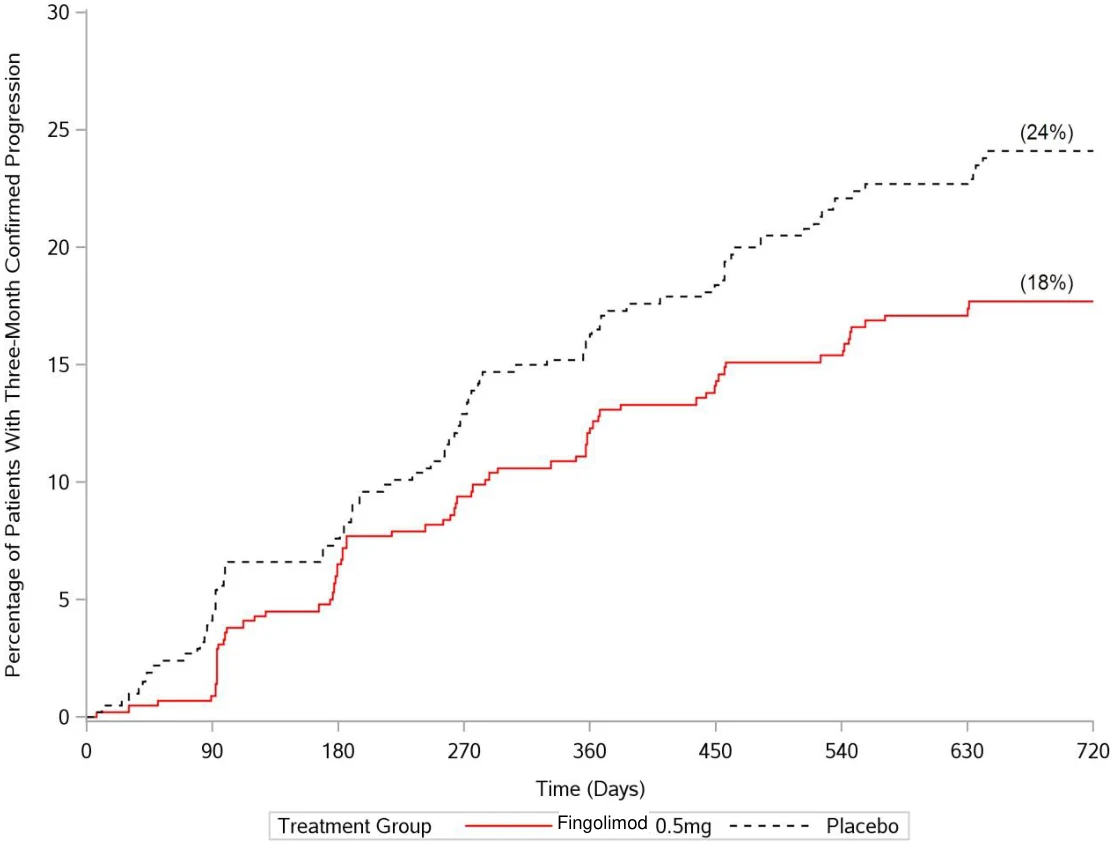
p = 0.026 for fingolimod vs. placebo.
The time to disability progression was significantly longer with fingolimod vs. placebo.
Fingolimod
Secondary MRI endpoints included new and enlarging (active) T2 lesion counts, T1 Gadolinium (Gd)-enhancing lesion count and the rate of brain atrophy. The mean number of active T2 lesions over 24 months was 2.5 for fingolimod 0.5 mg and 9.8 for placebo (p<0.001), representing a 74% relative reduction. The mean number of Gd-enhancing lesions at Month 24 was 0.2 for fingolimod compared to 1.1 for placebo (p<0.001), a relative reduction of 81%. The rate of brain atrophy (mean % change in total brain volume) was less with fingolimod (-0.8%) than with placebo (-1.3%) over 24 months (p<0.001). Changes in brain volume were also significant at Months 6 and 12.
Study D2302 (TRANSFORMS)
The TRANSFORMS study was a 1-year randomized, double-blind, double-dummy, active (interferon beta-1a)-controlled Phase III study in patients with relapsing-remitting multiple sclerosis who had not received any natalizumab in the previous 6 months. Prior treatment with interferon-beta or glatiramer acetate up to the time of randomization was permitted.
Neurological evaluations were performed at Screening, every 3 months and at the time of suspected relapses. MRI evaluations were performed at Screening and at month 12. The primary endpoint was the annualized relapse rate.
Median age was 36 years, median disease duration was 5.9 years and median EDSS score at baseline was 2.0. Approximately 57% of patients had received treatment with other disease modifying therapies prior to entering the study, with interferon-beta being the most commonly used prior treatment (used by 49% of all patients). Patients were randomized to receive fingolimod 0.5 mg (n=429) or 1.25 mg (n=420) or interferon beta-1a 30 micrograms via the intramuscular route once weekly (n=431) for up to 12 months. Median time on study drug was 365 days on 0.5 mg, 364 days on 1.25 mg and 361 days on interferon beta-1a.
The annualized relapse rate was significantly lower in patients treated with fingolimod than in patients who received interferon beta-1a, with a relative reduction in relapse of 52% for patients treated with fingolimod. The 1.25 mg dose did not provide additional benefit over the 0.5 mg dose.
The key secondary endpoints were the number of new or newly enlarging T2 lesions and the time to onset of 3-month confirmed disability progression as measured by at least a 1-point increase from baseline in EDSS (0.5 point increase for those with baseline EDSS of 5.5) sustained for 3 months. The number of new or newly enlarging T2 lesions was significantly lower in patients treated with fingolimod than in patients who received interferon beta-1a. There was no significant difference in the time to 3-month confirmed disability progression between fingolimod and interferon beta-1a-treated patients at 1 year. There were no significant differences between the 0.5 mg and the 1.25 mg doses on either endpoint. Results for the primary and key secondary endpoints of this study are shown in Table 4.
Table 5. TRANSFORMS study results
Fingolimod 0.5 mg | Interferon-beta-1a 30 μg | p-value | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| N=429 | N=431 | |||||||||
Primary endpoint Annualized relapse rate1 | 0.16 | 0.33 | <0.001 | |||||||
| Key secondary endpoints | ||||||||||
MRI Mean (median) number of new or newly enlarging T2 lesions over 12 months2 | 1.6 (0) | 2.6 (1.0) | 0.002 | |||||||
| 3-month confirmed disability progression Kaplan-Meier estimate of percentage (SE) of patients free of 3-month confirmed disability progression at Month 12 | 94.1 (1.25) | 92.1 (1.33) | 0.24 | |||||||
| Hazard ratio of disability progression (95% CI) | 0.71 (0.42, 1.21) | 0.21 | ||||||||
1 Based on confirmed relapses. Relapse was defined as neurologic symptoms together with an increase > 0.5 in the total EDSS score, or an increase of 1 point in each of two EDSS functional system scores, or an increase of two points in one EDSS functional system score (excluding bowel-bladder or cerebral functional systems). P-value determined by negative binomial regression adjusting for treatment, country, number of relapses in previous 2 years and baseline EDSS.
2 Statistical analysis using negative binomial regression adjusted for treatment, country, number of relapses in previous 2 years and baseline EDSS.
Other secondary endpoints included the proportion of patients remaining relapse-free, T1 Gd- enhancing lesion count and the rate of brain atrophy. The proportion of patients remaining relapse-free after 12 months was 83% for fingolimod 0.5mg and 70% for those receiving interferon beta-1a (p<0.001). The mean number of Gd-enhancing lesions at Month 12 was 0.2 for fingolimod compared to 0.5 for interferon beta-1a (p<0.001), a relative reduction of 60%. The rate of brain atrophy (mean % change in total brain volume) was less with fingolimod (-0.3%) than with interferon beta-1a (-0.5%) over 12 months (p<0.001).
Pooled results of studies D2301 and D2302 showed a consistent reduction of annualized relapse rate compared to comparator in subgroups defined by gender, age, prior multiple sclerosis therapy, disease activity or disability levels at baseline.
DETAILED PHARMACOLOGY
Mechanism of Action
Fingolimod-phosphate binding to S1P receptors on lymphocytes causes internalization and functional antagonism of S1P receptors. This reduces S1P-dependent egress of lymphocytes from lymphoid organs and, in animals reduces the numbers of autoreactive cells that invade the CNS. Studies in animals and in vitro studies indicate that fingolimod can penetrate the CNS and may also act via interaction with S1P receptors on neural cells.
Non-Clinical Pharmacokinetics
Pharmacokinetics and disposition of fingolimod, its metabolites, and fingolimod-phosphate (in the form of its (S)- and (R)-enantiomers AML629 and AML627, respectively) were investigated in mice, rats, rabbits, dogs and cynomolgus monkeys.
Fingolimod and fingolimod-phosphate were major drug-related components across all species including human. The fate of fingolimod and fingolimod-phosphate appears to be similar in all species investigated including man. Fingolimod-phosphate was present exclusively in the form of the (S)-enantiomer. The absolute oral bioavailability of fingolimod was high or up to complete in animals and humans. Systemic exposure to fingolimod was generally dose proportional with no gender differences. Fingolimod accumulated in the brain of rats, and dogs, and in the brain and lung of cynomolgus monkeys after multiple oral dosing. After discontinuation of dosing, fingolimod was slowly eliminated from the rat and monkey brain.
The biotransformation of fingolimod in animals and human occurred by three main pathways: (i) by reversible stereoselective phosphorylation to the (S)-enantiomer of fingolimod-phosphate, (ii) by hydroxylation at the terminal methyl group of the octyl chain (catalyzed predominantly by CYP4F2), followed by rapid further oxidation to the carboxylic acid metabolite which undergoes further biotransformation by β-oxidation-like losses of two carbon units to other carboxylic acid metabolites, (iii) formation of non-polar ceramide analogs of fingolimod. Essentially the same metabolites of fingolimod in humans were formed by at least one of the animal species in vivo and/or in vitro, supporting the selection of the toxicological test species.
Fingolimod was eliminated predominantly by oxidative metabolism (CYP4F2). Fingolimod- phosphate appeared to be eliminated mainly by de-phosphorylation back to fingolimod. Direct oxidation of fingolimod-phosphate does not appear to occur to a significant extent across species including human. Renal excretion of unchanged fingolimod was not observed. Fecal excretion of unchanged fingolimod and fingolimod-phosphate was minor.
The involvement of multiple cytochrome P450 isoenzymes in the oxidation of fingolimod suggests that the metabolism of fingolimod may not be readily inhibited completely by a single specific CYP inhibitor. The potential for drug-drug interactions between fingolimod and co- medications via cytochrome P450 enzymes, and via hepatic uptake and efflux transport systems appears low. Fingolimod and AML629 are not expected to inhibit cytochrome P450-mediated metabolic clearance of co-medications. Fingolimod does not induce its own liver drug metabolizing enzymes or those of potential co-medications.
Safety Pharmacology
A slight inhibition of hERG (25% or 18%) was present at the solubility limit of fingolimod or of the pharmacologically active S-enantiomer (0.5 μM or 0.4 μM) in stably transfected HEK293 cells.
In the Langendorff perfused rabbit heart model, fingolimod-phosphate increased cycle length and reduced coronary perfusion at target concentrations between 10 nM and 100 nM.
Oral fingolimod at 10 mg/kg induced significant decreases in heart rate, and increases in systolic and diastolic blood pressure in conscious, free-moving male cynomolgus monkeys.
Intravenous administration of the pharmacologically active S-enantiomer of fingolimod- phosphate decreased heart rate, decreased blood pressure, prolonged the PR interval, and caused sinus arrhythmias at doses of 0.01 and 0.1 mg/kg in anesthetized guinea pigs. The decrease in heart rate and prolongation of the PR interval caused by the S-enantiomer of fingolimod- phosphate were inhibited by pertussis toxin, suggesting the involvement of a Gαi/o-coupled S1P receptor.
In anesthetized rats intravenous fingolimod-phosphate decreased the heart rate and produced sinus arrhythmias at 0.3 mg/kg, prolonged the PR interval and decreased the respiratory tidal volume at doses greater than 0.03 mg/kg, and decreased respiratory minute volume at 0.03 mg/kg. Pertussis toxin inhibited the fingolimod-phosphate-induced decrease in heart rate, prolongation in PR interval, AV block and decrease in respiratory tidal volume.
Dyspnea, bradycardia and ECG findings of sino-atrial block, atrioventricular block, findings resembling left bundle branch block, atrial premature complexes, and ventricular premature complexes were present at 0.1 and/or 0.5 mg/kg in rats intravenously administered the pharmacologically active S-enantiomer of fingolimod-phosphate.
In dogs, by step-wise increasing the daily oral dose of fingolimod from 0.1 to 10 mg/kg, the decrease in heart rate and increase in blood pressure were less pronounced compared with giving an oral dose of ≥2.5 mg/kg on Day 1. An increase in frequency of AV block and ventricular premature contractions occurred in dogs given 10 mg/kg fingolimod orally.
Intravenous fingolimod (3 and 10 mg/kg) induced a marked and long-lasting increase in airway resistance in anesthetized rats. Pretreatment with B. pertussis toxin resulted in a reduction of the acute bronchoconstriction suggesting that the acute effects caused by fingolimod occur via signaling pathways involving Gi-GTP-binding protein.
Bronchoconstriction induced in anesthetized rats by IV injection of fingolimod was reversed by injection of the beta-2 adrenoceptor agonist, salbutamol.
TOXICOLOGY
The preclinical safety profile of fingolimod was assessed in mice, rats, dogs and monkeys.
Fingolimod had a moderate level of acute toxicity. Deaths occurred following single dose IV administration of 50 mg/kg in mice and ≥25 mg/kg IV in rats, and following single dose oral administration of ≥300 mg/kg in rats. No deaths occurred in dogs after single oral doses of 1000 or 2000 mg/kg. Signs of acute toxicity were referable to respiratory, CNS and gastrointestinal systems and included dyspnea, uncoordination, tremors, convulsions, sedation and decreased locomotor activity and forestomach ulcers in rodents, and vomiting and loose stools in dogs.
The major target organs in repeat-dose oral studies were lungs, and blood vessels with findings at administered dose levels and systemic exposures in animals that, in some instances, were without a defined margin compared with the human oral dose (0.5 mg/day) and associated systemic exposure.
Effects on the lymphoid system consisting of lymphopenia, lymphoid depletion (thymus cortex, spleen, lymph nodes), and increased size and density of staining of thymus medulla, were consistently observed across a wide range of doses in all animal species tested and essentially represent anticipated effects based on fingolimod pharmacology. Gastrointestinal protozoan infection was considered to reflect increased susceptibility to infection secondary to immunosuppression in monkeys administered 0.5 or 3 mg/kg. Granulomatous inflammation in lungs of mice and pneumonia observed in rats and dogs may also be secondary to immunosuppression.
Lung was a sensitive target organ in all animal species tested. Findings included increased lung weight and insufficient or lack of pulmonary collapse at necropsy. Microscopic lung changes included smooth muscle hypertrophy/hyperplasia and/or interstitial collagenization at the bronchoalveolar junction; hyperdistension of alveoli; and increased alveolar macrophage infiltrates. Lung pathologic changes occurred at ≥0.1 mg/kg in rats, ≥0.01 mg/kg in dogs, and
≥0.5 mg/kg in monkeys. In the 52-week monkey study respiratory distress was associated with ketamine administration at fingolimod doses of 3 and 10 mg/kg.
Vasculopathy in Wistar rats involved vessels in multiple organs including kidney, spleen, mesentery and brain. The lowest effect dose levels were 1.5 mg/kg in the 26-week study and
0.15 mg/kg in the 104-week carcinogenicity study. Vascular lesions in heart of dogs administered ≥1 mg/kg were considered related to hemodynamic effects of fingolimod.
Treatment-related kidney findings (nephropathy, tubular basophilia and/or hyaline casts) occurred in rodent studies (5 mg/kg in 13-week and ≥0.25 mg/kg in 104-week studies in mice;
≥0.3 mg/kg in 26-week and ≥0.05 mg/kg in 104-week studies in rats).
Pathologic changes were present in the nervous system in dogs at relatively high dose levels. Mononuclear cell infiltrates or perivascular mononuclear cells were present in brain or spinal cord at 10 mg/kg (26-week study) and 30 mg/kg (4-week study).
Treatment-related findings in repeat-dose toxicology studies generally showed evidence of potential reversibility following treatment withdrawal, although recovery was incomplete in some instances.
Effects on liver (increased transaminases in rats and dogs), pituitary (vacuolation and/or atrophy of anterior pituitary cells in rats and dogs), adrenal medulla (vacuolation and decrease in number of cells and fibrosis in dogs) and gastrointestinal tract (forestomach erosion in rats, stomach ulcers in dogs) mainly occurred at relatively high dose levels and inconsistently across species.
There were no treatment-related ophthalmoscopic findings in toxicology studies. Vasculopathy was present in eyes histopathologically for a small number of treated animals at ≥0.5 mg/kg in the 104-week rat study.
No evidence of carcinogenicity was observed in a 2-year bioassay in rats at oral doses of fingolimod up to the maximum tolerated dose of 2.5 mg/kg, representing an approximate 50-fold margin based on human systemic exposure (AUC) at the 0.5 mg dose. Vasculopathy and nephropathy were the main lesions contributing to the increased mortality at 0.5 and 2.5 mg/kg. In a 2-year mouse study, an increased incidence of malignant lymphoma was seen at doses of
0.25 mg/kg and higher, representing an approximate 6-fold margin based on human systemic exposure (AUC) at a daily dose of 0.5 mg.
Fingolimod was not mutagenic in an Ames test and in a L5178Y mouse lymphoma cell line in vitro. No clastogenic effects were seen in vitro in V79 Chinese hamster lung cells. Fingolimod induced numerical (polyploidy) chromosomal aberrations in V79 cells at concentrations of 3.7
µg/mL and above. Fingolimod was not clastogenic in the in vivo micronucleus tests in mice and rats.
Fingolimod had no effect on sperm count or motility, nor on fertility in male and female rats up to the highest dose tested (10 mg/kg), representing an approximate 150-fold margin based on human systemic exposure (AUC) at a daily dose of 0.5 mg.
Fingolimod was teratogenic at doses of 0.1 mg/kg or higher (corresponding to 2 or more times the exposure in humans at the recommended dose of 0.5 mg) when given to pregnant rats during the period of organogenesis. The most common fetal visceral malformations included persistent truncus arteriosus and ventricular septum defect. The receptor affected by fingolimod (sphingosine -1-phosphate receptor) is known to be involved in vascular formation during embryogenesis. An increase in post-implantation loss was observed in rats at doses of 1 mg/kg and higher and a decrease in viable fetuses at 3 mg/kg. Fingolimod was not teratogenic in the rabbit, but an increased incidence of embryo-fetal mortality was seen starting at doses of 1.5 mg/kg (corresponding to similar exposure in humans at the recommended dose of 0.5 mg), and a decrease in viable fetuses as well as fetal growth retardation at 5 mg/kg.
In rats, F1 generation pup survival was decreased in the early postpartum period at doses administered during pregnancy and lactation that did not cause maternal toxicity (0.05, 0.15 and
0.5 mg/kg). However, F1 body weights, development, behavior, and fertility were not affected by treatment with fingolimod.
Fingolimod was excreted in the milk of treated animals during lactation. Fingolimod and its metabolites crossed the placental barrier in pregnant rabbits.
REFERENCES
- 1. Brinkmann V. FTY720 (fingolimod) in Multiple Sclerosis: therapeutic effects in the immune and the central nervous system. Br J Pharmacol, 2009 158(5):1173-82.
- 2. Chitnis T, Arnold D.L, Banwell B, et al. Trial of Fingolimod versus Interferon Beta-1a Pediatric Multiple Sclerosis. N Engl J Med, 2018 379(11):1017-27.
- 3. Choi JW, Gardell SE, Herr DR, et al. FTY720 (fingolimod) efficacy in an animal model of multiple sclerosis requires astrocyte sphingosine 1-phosphate receptor 1 (S1P1) modulation. Proc Natl Acad Sci U S A, 2011; 108(2):751-6.
- 4. Chun J, Hartung HP. Mechanism of Action of Oral Fingolimod (FTY720) in Multiple Sclerosis. Clin Neuropharmacol, 2010; 33(2):91-101.
- 5. Cohen JA, Barkhof F, Comi G, et al. Oral fingolimod or intramuscular interferon for relapsing multiple sclerosis. N Engl J Med, 2010; 362(5):402-15.
- 6. David OJ, Ocwieja M, Meiser K, et al. Pharmacokinetics of fingolimod (FTY720) and a combined oral contraceptive coadministered in healthy women: drug-drug interaction study results. Int J Clin Pharmacol Ther, 2012; 50(8):540-4.
- 7. Foster CA, Howard LM, Schweitzer A, et al. Brain penetration of the oral immunomodulatory drug FTY720 and its phosphorylation in the central nervous system during experimental autoimmune encephalomyelitis: consequences for mode of action in multiple sclerosis. J Pharmacol Exp Ther, 2007; 323(2):469-75.
- 8. Fujino M, Funeshima N, Kitazawa Y, et al. Amelioration of experimental autoimmune encephalomyelitis in Lewis rats by FTY720 treatment. J Pharmacol Exp Ther, 2003; 305:70- 77.
- 9. Jaillard C, Harrison S, Stankoff B, et al. Edg8/S1P5: an oligodendroglial receptor with dual function on process retraction and cell survival. J Neurosci, 2005; 25(6):1459-1469.
- 10. Kappos L, Radue EW, O'Connor P, et al. A placebo-controlled trial of oral fingolimod in relapsing multiple sclerosis. N Engl J Med, 2010; 362(5):387-401.
- 11. Kimura A, Ohmori T, Ohkawa R, et al. Essential roles of sphingosine 1-phosphate/S1P1 receptor axis in the migration of neural stem cells toward a site of spinal cord injury. Stem Cells, 2007; 25(1):115-124.
- 12. Mandala S, Hajdu R, Bergstrom J, et al. Alteration of lymphocyte trafficking by sphingosine-1-phosphate receptor agonists. Science, 2002 296(5566):346-349.
- 13. Matloubian M, Lo CG, Cinamon G, et al. Lymphocyte egress from thymus and peripheral lymphoid organs is dependent on S1P receptor 1. Nature, 2004; 427(6972):355-360.
- 14. Miron VE, Schubart A, Antel JP. Central nervous system-directed effects of FTY720 (fingolimod). J Neurol Sci, 2008; 274(1-2):13-17.
- 15. Miron VE, Jung CG, Kim HJ, et al. FTY720 modulates human oligodendrocyte progenitor process extension and survival. Ann Neurol, 2008; 63(1):61-71.
- 16. Mizugishi K, Yamashita T, Olivera A, et al. Essential role for sphingosine kinases in neural and vascular development. Mol Cell Biol, 2005; 25(24):11113-11121.
- 17. Pham TH, Okada T, Matloubian M, et al. S1P1 receptor signaling overrides retention mediated by G alpha i-coupled receptors to promote T-cell egress. Immunity, 2008; 28:122- 33.
- 18. Schwab SR, Cyster JG. Finding a way out: lymphocyte egress from lymphoid organs. Nat Immunol, 2007; 8(12):1295-301.
- 19. GILENYA (fingolimod hydrochloride) Product Monograph by Novartis Pharmaceuticals Canada Inc., Date of Revision: December 19, 2019, Control No. 233920.