


Product Monograph - Auro-Bilastine
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES………………………………........………………………….2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ................................................................ 4
- 1.
INDICATIONS ......................................................................................................................... 4
1.1 Pediatrics ................................................................................................................... 4
1.2 Geriatrics ................................................................................................................... 4
- 2. CONTRAINDICATIONS ......................................................................................................... 4
- 4.
DOSAGE AND ADMINISTRATION ........................................................................................ 4
4.1 Dosing Considerations .............................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ......................................................... 5
4.4 Administration ............................................................................................................ 5
4.5 Missed Dose .............................................................................................................. 5
- 5. OVERDOSAGE ........................................................................................................... 5
- 6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................... 6
- 7.
WARNINGS AND PRECAUTIONS ........................................................................... 6
7.1 Special Populations ................................................................................................... 7
7.1.1 Pregnant Women .................................................................................................. 7
7.1.2 Breast-feeding ....................................................................................................... 7
7.1.3 Pediatrics (<12 years of age) ................................................................................ 8
7.1.4 Geriatrics (>65 years of age) ................................................................................. 8
- 8.
ADVERSE REACTIONS ........................................................................................................ 8
8.1 Adverse Reaction Overview ...................................................................................... 8
8.2 Clinical Trial Adverse Reactions ................................................................................ 8
8.3 Less Common Clinical Trial Adverse Reactions........................................................ 9
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ...................................................................................................... 10
8.5 Post-Market Adverse Reactions .............................................................................. 10
- 9.
DRUG INTERACTIONS ....................................................................................................... 10
9.2 Drug Interactions Overview ..................................................................................... 10
9.3 Drug-Behavioral Interactions ................................................................................... 11
9.4 Drug-Drug Interactions ............................................................................................ 11
9.5 Drug-Food Interactions ............................................................................................ 11
9.6 Drug-Herb Interactions ............................................................................................ 12
9.7 Drug-Laboratory Test Interactions ........................................................................... 12
- 10.
CLINICAL PHARMACOLOGY ........................................................................................... 12
10.1 Mechanism of Action ............................................................................................. 12
10.2 Pharmacodynamics ............................................................................................... 12
10.3 Pharmacokinetics .................................................................................................. 14
- 11. STORAGE, STABILITY AND DISPOSAL .......................................................................... 16
- 12. SPECIAL HANDLING INSTRUCTIONS ............................................................................. 16
PART II: SCIENTIFIC INFORMATION ..................................................................................... 17
- 13. PHARMACEUTICAL INFORMATION ................................................................................ 17
- 14.
CLINICAL TRIALS ............................................................................................................. 18
14.1 Trial Design and Study Demographics .................................................................. 18
14.2 Study Results ........................................................................................................ 19
14.3 Comparative Bioavailability Studies ...................................................................... 22
- 15. NON-CLINICAL TOXICOLOGY ......................................................................................... 22
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 24
PATIENT MEDICATION INFORMATION ................................................................................. 25
PART I: HEALTH PROFESSIONAL INFORMATION
1. INDICATIONS
Seasonal Allergic Rhinitis
Auro-Bilastine (bilastine) is indicated for the symptomatic relief of nasal and non-nasal symptoms of seasonal allergic rhinitis (SAR) in patients 12 years of age and older.
Chronic Spontaneous Urticaria
Auro-Bilastine (bilastine) is indicated for the relief of the symptoms associated with chronic spontaneous urticaria (CSU) (e.g. pruritus and hives), in patients 12 years of age and older.
1.1 Pediatrics
Pediatrics (< 12 years of age): Auro-Bilastine should not be administered to children below 12 years of age. Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Auro-Bilastine tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (> 65 years of age): No dosage adjustments are necessary in patients over 65 years (see ACTION AND CLINICAL PHARMACOLOGY, DOSAGE AND ADMINISTRATION).
2. CONTRAINDICATIONS
Auro-Bilastine is contraindicated in patients with:
- hypersensitivity to bilastine or to any ingredient in the formulation or component of the container. For a complete listing of ingredients and components (see Dosage Forms, Strengths, Composition and Packaging).
- a history of QT prolongation and/or torsade de pointes, including congenital long QT syndromes (see WARNINGS AND PRECAUTIONS, DRUG INTERACTIONS, ACTION AND CLINICAL PHARMACOLOGY).
4. DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Renal impairment
No dosage adjustments are required in subjects with renal impairment.
Hepatic impairment
There is no clinical experience in subjects with hepatic impairment. Since bilastine is not metabolized and renal clearance is the major route of elimination, hepatic impairment is not expected to increase systemic exposure above the safety margin. Therefore, no dosage adjustment is required in subjects with hepatic impairment.
Pediatrics (<12 years of age)
Auro-Bilastine tablets should not be administered to children below 12 years of age.
Geriatrics (> 65 years of age)
No dosage adjustments are recommended in subjects > 65 years of age.
4.2 Recommended Dose and Dosage Adjustment
Recommended daily dose:
| Seasonal Allergic Rhinitis | ≥12 years | 20 mg (1 tablet) once daily |
|---|---|---|
| Chronic Spontaneous Urticaria | ≥12 years | 20 mg (1 tablet) once daily |
Maximum daily dose
≥12 years
The maximum recommended daily dose is 20 mg (1 tablet) and should not be exceeded.
4.4 Administration
20 mg tablet
One 20 mg tablet of Auro-Bilastine once daily should be swallowed with water on an empty stomach to achieve optimal exposure to bilastine. The Auro-Bilastine tablet should be taken without food or grapefruit juice or other fruit juices, as these dietary compounds may decrease the effect of bilastine. Patients should be instructed to take the tablet and wait for one hour before taking food or fruit juice, or if food or fruit juice has been taken, to wait for two hours before taking the tablet.
4.5 Missed Dose
If a dose is missed, the next scheduled dose should be taken. An extra dose should not be taken.
5. OVERDOSAGE
Information regarding acute overdose is limited to experience from clinical trials conducted during the development of bilastine. After administration of bilastine at doses 10 to 11 times the therapeutic dose (220 mg (single dose); or 200 mg/day for 7 days) to healthy volunteers frequency of treatment emergent adverse events was two times higher than with placebo. The adverse reactions most frequently reported were dizziness, headache and nausea. No serious adverse events and no significant prolongation in the QTc interval were reported. There are no data for overdose in children.
Electrocardiogram monitoring is recommended in the event of overdosage (see WARNINGS AND PRECAUTIONS, ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics).
Overdose in the post-marketing setting has been reported rarely; any adverse events were consistent with those seen in clinical trials.
In the event of overdose, symptomatic and supportive treatment is recommended. There is no known specific antidote to bilastine.
6. DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| oral | tablet, 20 mg | colloidal anhydrous silica, magnesium stearate, microcrystalline cellulose and sodium starch glycolate. |
Composition
20 mg tablet
Auro-Bilastine tablets are Oval shaped, debossed with BN & 2 separated with break line on one side and plain on other side. Each tablet contains 20 mg of active ingredient, bilastine.
The score line is only to facilitate breaking for ease of swallowing and not to divide into equal doses.
Packaging
20 mg tablet
Auro-Bilastine 20 mg tablets are available in HDPE bottles of 100’s and 3 x 10’s tablets blister packs in a carton.
7. WARNINGS AND PRECAUTIONS
Cardiovascular
Bilastine has been associated with QTc interval prolongation (see ACTION AND CLINICAL PHARMACOLOGY, Cardiac Electrophysiology). Drugs that cause QT/QTc prolongation are suspected of increasing the risk of torsade de pointes. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QT/QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Auro-Bilastine should not be used in patients with a history of QTc prolongation and/or torsade de pointes, including congenital long QT syndromes (see CONTRAINDICATIONS).
Particular care should be exercised when administering antihistamines, including Auro-Bilastine to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug. This includes patients who have a
For management of a suspected drug overdose, contact your regional poison control centre.
history of cardiac arrhythmias; hypokalemia; hypomagnesaemia; significant bradycardia; family history of sudden cardiac death; concomitant use of other QT/QTc-prolonging drugs.
When drugs that prolong the QTc interval are prescribed, healthcare professionals should counsel their patients concerning the nature and implications of the ECG changes, underlying diseases and disorders that are considered to represent risk factors, demonstrated and predicted drug-drug interactions, symptoms suggestive of arrhythmia, risk management strategies, and other information relevant to the use of the drug.
Driving and Operating Machinery
A study was performed to assess the effects of bilastine 20 mg and bilastine 40 mg on real time driving performance compared to placebo and hydroxyzine 50 mg. Bilastine did not affect driving performance differently than placebo following day one or after one week of treatment. However, patients should be informed that very rarely some people experience drowsiness, which may affect their ability to drive or use machines.
Hepatic
Bilastine has not been studied in subjects with hepatic impairment. Since bilastine is not metabolized and renal clearance is the major route of elimination, hepatic impairment is not expected to increase systemic exposure above the safety margin.
Renal
In subjects with moderate or severe renal impairment co -administration of bilastine with P- glycoprotein inhibitors, such as ketoconazole, erythromycin, cyclosporine, ritonavir or diltiazem, may increase plasma levels of bilastine and therefore increase the risk of adverse effects. Co-administration of bilastine and P-glycoprotein inhibitors should be avoided in subjects with moderate or severe renal impairment.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. Until such data become available, Auro-Bilastine should be avoided during pregnancy, unless advised otherwise by a physician.
Animal studies do not indicate major direct or indirect harmful effects with respect to reproductive toxicity, parturition or postnatal development (see TOXICOLOGY).
Twelve (12) pregnancies were reported during bilastine investigation. Follow-up was performed by the investigators through to the birth of newborns. Their observations indicated that there had been a normal outcome reported for every pregnancy, except one miscarriage due to an antiphospholipid syndrome (case history of repeated miscarriages) resulting in an induced abortion (voluntary).
7.1.2 Breast-feeding
The excretion of bilastine in milk has not been studied in humans. Available pharmacokinetic data in animals have shown excretion of bilastine in milk. A decision on whether to continue/discontinue breast-feeding or to continue/discontinue therapy with Auro-Bilastine should be made taking into account the benefit of breast-feeding to the child, the benefit of bilastine therapy to the mother, and these should be weighed against possible effects on the infant.
7.1.3 Pediatrics (<12 years of age)
Auro-Bilastine should not be administered to children below 12 years of age.
7.1.4 Geriatrics (>65 years of age)
No dosage adjustments are recommended in subjects over 65 years of age (see ACTION AND CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION).
8. ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The clinical safety of bilastine was evaluated in 10 Phase 2 and 3 studies performed in 2186 adult and adolescent subjects with allergic rhinitis, or chronic spontaneous urticaria (CSU), where bilastine was used at doses ranging from 10 – 40 mg over treatment periods of 2 – 4 weeks.
The most common treatment-emergent adverse reactions reported in the double-blind Phase 3 studies involving 931 subjects treated with bilastine 20 mg were related to the central nervous system (headache, dizziness, and somnolence) and the gastrointestinal system (abdominal pain upper).
Treatment-emergent cardiovascular effects occurred infrequently or rarely (bundle branch block right sinus arrhythmia, sinus bradycardia and ventricular extrasystoles, abnormal ECG investigations) in clinical studies.
A one year open-label safety study in 513 allergic rhinitis patients was conducted with bilastine 20 mg tablets. The most common adverse events seen in this open-label study were headache, influenza, and nasopharyngitis.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adolescents and Adults
At the recommended dose of 20 mg daily, treatment-emergent adverse reactions with bilastine were equal to those treated with placebo. The most commonly reported related AEs were dizziness, headache and somnolence.
The incidence of treatment-emergent adverse reactions reported by ≥1% of subjects treated with bilastine in Phase 2 and 3 trials is presented in Table 2.
Table 2 Treatment-Emergent Adverse Reactions Reported in ≥ 1% of Subjects Treated with Bilastine in the Double-Blind Studies
| Body System / AE | Bilastine N=931 | Placebo N=950 |
|---|---|---|
| Gastrointestinal disorders | 28 (3.01%) | 28 (2.95%) |
| Abdominal pain upper | 10 (1.07%) | 4 (0.42%) |
| Nervous system disorders | 81 (8.70%) | 55 (5.79%) |
| Dizziness | 10 (1.07%) | 4 (0.42%) |
| Headache | 40 (4.30%) | 28 (2.95%) |
| Somnolence | 38 (4.08%) | 25 (2.63%) |
The incidence of adverse events in adult and adolescent patients suffering from allergic rhinoconjunctivitis or chronic spontaneous urticaria treated with 20 mg bilastine in clinical trials was comparable with the incidence in patients receiving placebo (12.7% versus 12.8%).
Long term open-label study:
The adverse event profile in the long term follow up study (1 year) in 513 patients demonstrated a similar profile to that observed in the controlled 2 -4 week Phase 2 and 3 clinical studies (see Adverse Reactions Overview).
8.3 Less Common Clinical Trial Adverse Reactions
The following events were observed in < 1% of 2186 patients treated with bilastine in Phase 2 and 3 clinical studies.
Blood and lymphatic system disorders: Anaemia
Cardiovascular: Bundle branch block right, sinus arrhythmia, sinus bradycardia, ventricular extrasystoles
- ECG investigations: electrocardiogram QT prolonged, electrocardiogram ST -T segment abnormal, electrocardiogram T wave abnormal, electrocardiogram T wave inversion, electrocardiogram abnormal, QRS axis abnormal
Ear and labyrinth disorders: Motion sickness, tinnitus, vertigo
Eye disorders: Eye pain
Gastrointestinal disorders: Abdominal pain, constipation, diarrhoea, dry mouth, dysgeusia, dyspepsia, eructation, gastritis, nausea, stomach discomfort, tongue dry, vomiting
General disorders and administration site conditions: Asthenia, chest discomfort, discomfort, fatigue, feeling jittery, pain, pyrexia, thirst
Infections and infestations: Oral herpes, pharyngitis
Metabolism and nutrition disorders: Increased appetite
Musculoskeletal and connective tissue disorders: Back pain, muscular weakness, myalgia
Nervous system disorders: Disturbance in attention, hypersomnia
Psychiatric disorders: Anxiety, insomnia, nightmare
Reproductive system and breast disorders: Menstruation delayed
Respiratory, thoracic and mediastinal disorders: Dyspnoea, epistaxis, nasal discomfort, nasal dryness, throat irritation
Skin and subcutaneous tissue disorders: Dermatitis acneiform, pruritus, rash popular, urticaria
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Investigations: Alanine aminotransferase increased, aspartate aminotransferase increased, blood bilirubin increased, blood cholesterol increased, blood triglycerides increased, gamma -glutamyl transferase increased, weight decreased, weight increased
8.5 Post-Market Adverse Reactions
Because adverse events are spontaneously reported in a voluntary manner from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
The following adverse reactions have been observed during the post -marketing period: palpitations, tachycardia, hypersensitivity reactions (such as anaphylaxis, angioedema, dyspnoea, rash, localized edema/local swelling, and erythema).
A case of torsade de pointes has been reported following the use of bilastine when administered with concomitant medications known to have the potential for QT prolongation.
9. DRUG INTERACTIONS
9.2 Drug Interactions Overview
The psychomotor performance after concomitant intake of alcohol and bilastine was similar to that observed after intake of alcohol and placebo (see DETAILED PHARMACOLOGY / Human Pharmacodynamics / Psychomotor Pharmacodynamics).
Particular care should be exercised when administering antihistamines, including bilastine to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, DRUG INTERACTIONS, ACTION and CLINICAL PHARMACOLOGY).
9.3 Drug-Behavioral Interactions
A study was performed to assess the effects of bilastine 20 mg and bilastine 40 mg on real time driving performance compared to placebo and hydroxyzine 50 mg. Bilastine did not affect driving performance differently than placebo following day one or after one week of treatment. However, patients should be informed that very rarely some people experience drowsiness, which may affect their ability to drive or use machines.
9.4 Drug-Drug Interactions
Ketoconazole and erythromycin
Concomitant administration of bilastine 20 mg tablets and ketoconazole or erythromycin increased bilastine AUC 2-fold and Cmax 2-3 fold. These changes can be explained by interaction with intestinal efflux transporters, since bilastine is a substrate for P-gp and not metabolized.
In a randomised, double-blind, placebo- and positive-controlled, 5-way crossover ECG assessment study in 30 healthy adult subjects, bilastine 20 mg/day administered alone for four days was associated with statistically significant positive mean differences from placebo in the QTcF interval at 1 and 3 h post-dosing on day 4, with a maximum mean difference from placebo of 4.0 ms (90% CI 1.20, 6.73) at 1 h, whereas bilastine 20 mg/day and ketoconazole 400 mg administered concomitantly for four days produced statistically significant QTcF prolongation at all time points from 0.5-12 h, inclusive, on day 4 with a maximum mean difference from placebo of 10.0 ms (90% CI 6.49, 13.43) at 1 h. Other medicinal products that are substrates or inhibitors of P-gp, such as cyclosporine, may likewise have the potential to increase plasma concentrations of bilastine.
Diltiazem
Concomitant administration of bilastine 20 mg and diltiazem 60 mg increased Cmax of bilastine by 50%. This effect can be explained by interaction with intestinal efflux transporters and does not appear to affect the safety profile of bilastine.
Lorazepam
Concomitant intake of bilastine 20 mg and lorazepam 3 mg for 8 days did not potentiate the depressant CNS effects of lorazepam.
QTc-Prolonging Drugs:
The concurrent use of bilastine with other QTc prolonging drugs is not recommended.
Inhibitors of P-Glycoprotein:
Plasma levels of bilastine can be increased by inhibitors of P-glycoprotein; the concomitant use of these drugs with bilastine is not recommended. Drugs that inhibit P-glycoprotein include, but are not limited to certain azole antifungal, macrolide antibiotics, and HIV protease inhibitors (see WARNINGS AND PRECAUTIONS).
Drugs that Cause Electrolyte Depletion:
The use of bilastine with drugs that can cause electrolyte imbalance is not recommended (see WARNINGS AND PRECAUTIONS).
9.5 Drug-Food Interactions
20 mg tablet
Plasma bilastine Cmax, AUCT, and AUCI values were approximately 33%, 17%, and 18% lower, respectively, for subjects receiving bilastine following consumption of a high-fat, high calorie meal compared to bilastine administered under fasted conditions. Plasma bilastine Cmax, AUCT, and AUCI values were approximately 25%, 26%, and 25% lower, respectively, for subjects receiving bilastine following consumption of a low-fat, low calorie breakfast compared to bilastine administered under fasted conditions. The Phase 3 clinical trials were conducted under fasting conditions to ensure clinically appropriate exposure to bilastine.
Grapefruit Juice
Concomitant administration of bilastine and grapefruit juice decreased bilastine bioavailability by approximately 30%. Concomitant administration of bilastine with other fruit juices may also decrease bioavailability. The degree of bioavailability decrease may vary between producers and types of fruit juice. The mechanism for this interaction is an inhibition of OATP1A2, an uptake transporter for which bilastine is a substrate. Medicinal products that are substrates or inhibitors of OATP1A2, such as ritonavir or rifampicin, may likewise have the potential to decrease plasma concentrations of bilastine.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been studied.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been observed.
- 10. CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Bilastine is an antihistamine; its principal effects are mediated via selective inhibition of peripheral H1 receptors. The antihistaminic activity of bilastine has been documented in a variety of animal and human models. It shows moderate to high affinity for histamine H1- receptors and no affinity for muscarinic, serotonergic, dopaminergic and noradrenergic receptors. Bilastine has been demonstrated to have limited distribution to the brain following oral administration.
10.2 Pharmacodynamics
Nonclinical Pharmacology
Pharmacodynamics
Bilastine has shown selective antagonism of H1 receptor mediated effects in vitro, in isolated organs, and in vivo in nonclinical pharmacology studies In vitro, bilastine displaced the H1 receptor antagonist pyrilamine from the human recombinantly expressed H1 receptor with a Ki of 64 nM (30 ng/mL). Bilastine did not modify H2 and H3 mediated effects in isolated animal organs at 100 μM and 30 μM, respectively, and did not bind to human recombinant H4 receptors at 10 μM. In in vivo animal models of anaphylaxis, single dose oral administration of bilastine dose-dependently reduced the allergen-induced increase in capillary permeability with ED50 values of approximately 6 mg/kg. Bilastine showed no efficacy in mouse models of type III and IV hypersensitivity reactions.
Safety Pharmacology
Nonclinical safety pharmacology studies conducted with bilastine investigated the main organ systems, cardiovascular, pulmonary, and central nervous system, but also effects on the gastrointestinal system. In two separate studies, bilastine caused a concentration -dependent suppression of hERG tail currents in stably transfected HEK 293 cells with IC50 values of 6.5 µM and 17.17 µM, respectively, based on nominal concentrations. In the isolated guinea pig heart atrium, bilastine at a concentration of 100 µM did not affect heartbeat strength or frequency. In conscious telemetered dogs, bilastine given once orally at dose levels of 10, 30, or 100 mg/kg caused dose-dependent QTc prolongation at 30 and 100 mg/kg and reductions in systolic and diastolic blood pressure at the high dose only. Decreased heart rate and PR interval prolongation were also observed at 30 and 100 mg/kg. In a second study in dogs, no effect on these parameters was seen at the same dose levels. After a single oral dose, bilastine had minimal/ no effects on the central nervous system. An oral dose of 1,000 mg/kg transiently increased alertness in rats and 800 mg/kg caused a moderate decrease of motor activity in mice. Bilastine did not affect respiratory parameters at oral doses up to 1,000 mg/kg in rats.
Bilastine had no effect on gastric secretion after 100 mg/kg administered intraduodenally in the rat or on intestinal motility in the mouse after oral doses up to 300 mg/kg.
Clinical Pharmacology
Studies in adult healthy subjects showed that 20 mg bilastine inhibited the skin wheal and flare reactions induced with a histamine prick test for 24 hours, as well as the wheal and flare reactions in cold induced urticaria.
In an environmental chamber study, the onset of action of bilastine was demonstrated to be 1 hour after treatment administration and the effect lasted for 26 hours.
In controlled clinical trials at the recommended dose of 20 mg once daily, the CNS safety prof ile of bilastine was similar to placebo and the incidence of somnolence was not statistically different from placebo. Bilastine at doses of up to 40 mg once daily did not affect psychomotor performance in clinical trials and did not affect driving performance in a standard driving test.
Cardiac Electrophysiology: A randomized, double-blind, placebo- and positive-controlled, 5- way crossover study of the electrocardiographic effects of bilastine was performed in 30 healthy adult subjects. Bilastine was tested at a therapeutic dose of 20 mg/day and a supratherapeutic dose of 100 mg/day, each administered for four days.
The bilastine 20 mg/day and 100 mg/day treatments were associated with a concentration- related prolongation of the QTcF (QTcF=QT/RR1/3) interval. On day 4 of treatment with the therapeutic 20 mg/day dose, statistically significant positive mean differences from placebo were observed at 1 and 3 h post-dosing, with a maximum mean difference from placebo of 4.0 ms (90% CI 1.20, 6.73) at 1 h.
On day 4 of treatment with the supratherapeutic bilastine 100 mg/day dose, statistically significant QTcF prolongation was observed at 5 consecutive time points from 0.5 to 3 h post - dose, with a maximum mean difference from placebo of 6.0 ms (90% CI 2.59, 9.48) at 2 h (see CONTRAINDICATIONS, WARNINGS AND PRECAUTIONS, ADVERSE REACTIONS,
DRUG INTERACTIONS, OVERDOSAGE).
Bilastine administered at doses of 20 mg/day and 100 mg/day for four days was not observed to affect the QRS duration, the PR interval, or heart rate.
10.3 Pharmacokinetics
Pre-Clinical Pharmacokinetics
Bilastine is orally bioavailable in mice, rats, rabbits, and dogs. There is large interanimal variability in the plasma concentrations with some studies reporting multiple peaks after oral administration. In rats, exposure after gavage dosing appeared higher in females than in males. Distribution studies with 14C labelled bilastine in rat indicate limited peripheral distribution, in which concentrations of radioactivity were highest in the liver and kidney. In pigmented rats, detectable levels persisted in the eye and uveal tract for up to 14 days, indicating binding to melanin. In pregnant rats, there was low-level passage of radioactivity across the placental barrier into the tissues of the fetus. The mechanisms have not been elucidated, but pretreatment of rats with a potent P-gp inhibitor significantly increased exposure. Bilastine plasma protein binding was moderate with limited distribution into red cells. Bilastine is minimally metabolized in vitro and in vivo in animals. After oral dosing, bilastine was rapidly excreted in rats and dogs, with 7-12% and 4-6% of the dose was recovered in urine of rats and dogs, respectively, and the balance recovered in feces. In bile duct cannulated rats, 17% of the administered dose was excreted in the bile.
In a lactation study, bilastine was identified in the milk of nursing rats administered a single oral dose (20 mg/kg). Concentrations of bilastine in milk were about half of those in maternal plasma. The relevance of those results for humans is unknown.
Clinical Pharmacokinetics
Bilastine pharmacokinetics were studied following a single oral dose of 20 mg to healthy volunteers. The results are presented in Table 3 below.
Table 3 Bilastine pharmacokinetic parameters after a single oral dose of 20 mg (n=12)
| Parameter | Mean ± standard deviation |
|---|---|
| AUC (0-t) (ng*h/ml) | 993.99 ± 279.93 |
| AUC0-∞ (ng*h/ml) | 997.40 ± 279.81 |
| % AUC 0-∞ extrapolation | 0.37 ± 0.26 |
| Cmax (ng/mL) | 219.67 ± 62.06 |
| tmax (h)# | 1.13 ± (0.75-3) |
| t1/2 (h) | 5.47 ± 2.13 |
| Ae (mg) | 8.39 ± 4.70 |
| Clr (l/h) | 9.20 ± 7.35 |
#: median and range
The pharmacokinetic data obtained in 310 healthy volunteers enrolled in several Phase 1 studies were combined in a population pharmacokinetic two compartment model. t1/2β was 14.53 hrs, AUC was 1104.97 ng.h/mL and Cmax was 220.08 ng/mL, with a tmax of 1.29 h.
Absorption: Bilastine is rapidly absorbed after oral administration with a time to maximum plasma concentration of around 1.13 hours. No accumulation was observed in subjects treated with bilastine from 20 to 100 mg daily after 14 days. The absolute bioavailability of bilastine is 61%.
Administration of bilastine following consumption of a meal with a fat and calorie content ranging from low-fat, low calorie to high-fat, high calorie results in a significant decrease in Cmax, AUCT and AUCI [see DRUG INTERACTION, Drug-Food Interactions].
Distribution: In vitro and in vivo studies have shown that bilastine is a substrate of P-gp (see DRUG INTERACTIONS / Drug-Drug Interactions) and OATP (see DRUG INTERACTIONS / Drug-Food Interactions). Bilastine does not appear to be a substrate of the transporter BCRP or renal transporters OCT2, OAT1 and OAT3. Based on in vitro studies, bilastine is not expected to inhibit the following transporters in the systemic circulation: MRP2, BCRP, BSEP, OATP1B3, OATP2B1, OAT1, OAT3, OCT2 and NTCP. Mild inhibition was detected for P-gp, OATP2B1 and OCT1, with an estimated IC50 ≥300 µM, much higher than the calculated clinical plasma Cmax. However, based on these results inhibition by bilastine of transporters present in the intestinal mucosa, e.g. P-gp, cannot be excluded.
At therapeutic doses bilastine is 84-90% bound to plasma proteins.
Metabolism: Bilastine is not significantly metabolized in humans (see Excretion). Bilastine does not induce or inhibit activity of CYP450 isoenzymes in in vitro and in vivo studies. Studies examining hepatic tissues (microsomes and hepatocytes) of human origin using different doses of bilastine demonstrated that there was little to no interaction with CYP isoenzymes.
Elimination: In a mass balance study performed in healthy volunteers, after administration of a single dose of 20 mg 14C-bilastine, almost 95% of the administered dose was recovered in urine (28.3%) and faeces (66.5%) as unchanged bilastine. The mean elimination half-life calculated in healthy volunteers in the population pharmacokinetic model was 14.5 h.
Linearity: Bilastine presents linear pharmacokinetics in the dose range studied (5 to 220 mg), with a low inter-individual variability.
Special Populations and Conditions
Pediatrics: Auro-Bilastine should not be administered to children below 12 years of age.
Geriatrics: The safety and efficacy of bilastine have been demonstrated in a limited number of subjects > 65 years of age (n=34) enrolled in controlled clinical studies. A further open label study provided safety data for 150 patients treated for urticaria and/or allergic rhinitis. The pharmacokinetic parameters of bilastine are comparable in healthy subjects > 65 years of age and younger subjects, and no dosage adjustments are considered necessary in this patient population.
Sex: No statistically significant gender-related differences have been observed with regard to the pharmacokinetic parameters of bilastine.
Hepatic Insufficiency: There are no pharmacokinetic data in subjects with hepatic impairment. Bilastine is not significantly metabolized in humans, with the vast majority of the administered dose excreted unchanged. Since the results of the renal impairment study indicate renal elimination to be a major contributor in the elimination of bilastine, biliary excretion is expected to be only marginally involved. Changes in liver function are not expected to have a clinically relevant influence on bilastine pharmacokinetics.
Renal Insufficiency: A study of bilastine was performed in 24 male and female adults: 6 healthy controls and 6 each with mild, moderate, and severe renal impairment. The mean plasma bilastine concentrations in subjects with renal impairment generally exceeded those in the control group during the first 12 hours after dose administration. The subjects with renal impairment had higher mean bilastine AUC and Cmax values than the healthy subjects. The mean AUC0-∞ ranged from 737.4 to 1708.5 ng·hr/mL in healthy subjects and severely impaired subjects, respectively. The mean Cmax ranged from 144.0 to 271.1 ng/mL in healthy subjects and moderately impaired subjects, respectively. There did not appear to be any substantial differences in median Tmax or in the mean elimination rate constants for bilastine. Renal clearance was highest in healthy subjects, 8.7 L/hr and lowest in subjects with severe renal impairment, 4.0 L/hr. Urinary excretion of bilastine was essentially complete by the end of the 48 to 72 hour collection interval for all subjects, and the urinary excretion plots show essentially parallel excretion rate curves across groups.
- 11. STORAGE, STABILITY AND DISPOSAL
Recommended storage conditions: Store between 15°C – 30°C.
- 12. SPECIAL HANDLING INSTRUCTIONS
Keep out of reach and sight of children.
PART II: SCIENTIFIC INFORMATION
- 13. PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Bilastine
Chemical name: 2-[4-[2-[4-[1-(2-Ethoxyethyl)Benzimidazole-2-yl]Piperidine-1-yl]ethyl]phenyl]-2-methylpropanoic acid
Molecular formula and molecular mass: C28H37N3O3, 463.62 g/mol
Structural formula:
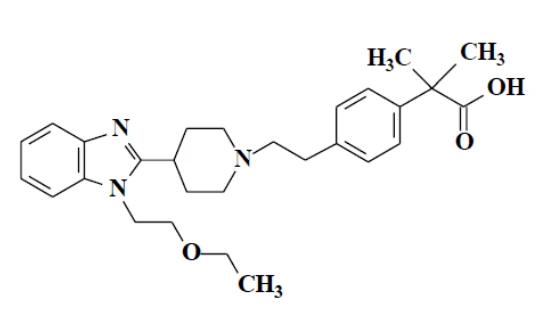
Physicochemical properties:
Physical Form: A white to off- white powder
Solubility: Freely soluble in 1N Sodium hydroxide solution, Slightly soluble in Methanol; Slightly to very slightly soluble in Water; Practically insoluble in Acetonitrile.
pKa Value: 4.4 and 9.1(Calculated using Chembio Software)
Hygroscopicity: Non-Hygroscopic in nature
14. CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Efficacy in Seasonal Allergic Rhinitis
Study demographics and trial design
The clinical efficacy of bilastine 20 mg tablets in the treatment of seasonal allergic rhinitis (SAR) was examined in three double-blind, randomized, placebo- and active-controlled parallel group clinical trials (BILA 1003/RAE, BILA 1704/RAE, and BILA 0802/RAE). A total of 2359 patients were randomized to treatment with bilastine, placebo or active comparator (desloratadine 5 mg and cetirizine 10 mg).
Table 4 Summary of patient demographics for clinical trials in seasonal allergic rhinitis
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
|---|---|---|---|---|---|
BILA 1003/RAE (Bachert et al, 2009) | Double-blind, randomized, placebo- and active- controlled parallel group | Bilastine 20 mg Desloratadine 5 mg Placebo Oral, once daily for 14 days | 233 242 245 ITT Total: 720 | 30 (12-70) | 121/112 126/116 118/127 |
BILA 1704/RAE (Kuna et al, 2009) | Double-blind, randomized, placebo- and active- controlled parallel group | Bilastine 20 mg Cetirizine 10 mg Placebo Oral, once daily, for 14 days | 226 227 225 ITT Total: 678 | 31 (12-69) | 108/118 107/120 108/117 |
| BILA 0802/RAE | Double-blind, randomized, placebo- and active- controlled parallel group | Bilastine 20 mg Bilastine 40 mg Cetirizine 10 mg Placebo Oral, once daily, for 14 days | 240 239 240 242 ITT Total: 961 | 35.1 (12-70) | 101/139 85/154 86/154 83/159 |
In the pivotal Phase 3 SAR studies the primary efficacy variable was the change in the area under the curve (AUC) of the total symptom score (TSS) from baseline to the end of the study (Day 14).
TSS was comprised of the reflective total nasal symptom score (rTNSS) and the reflective total non-nasal symptom score (rTNNSS).
rTNSS was based on the twice daily, AM and PM, reflective assessment of four nasal symptoms: rhinorrhea, nasal congestion, nasal itching, and sneezing, using a four point (0 [none] to 3 [severe]) scoring scale.
rTNNSS included four non-nasal symptoms: ocular itching, tearing, ocular redness, itching of ears and/or palate (the latter being scored only in study BILA 1003/RAE), and was assessed in a similar manner.
In one study, patients also recorded these symptoms in an instantaneous manner.
Change from baseline in rTNSS, rTNNSS, TSS, and Quality of Life (QofL) were assessed as secondary variables.
In two of the trials (BILA 1003/RAE & BILA 1704/RAE), bilastine demonstrated superior efficacy to placebo. In the third trial, BILA 0802/RAE, neither bilastine nor the active control, cetirizine, could be distinguished from placebo. Therefore, the results from this study are not presented here.
14.2 Study Results
BILA 1003/RAE
The primary efficacy end-point, change in AUC of TSS from baseline to the end of the study in bilastine-treated patients was statistically significantly different from placebo ( Table 5). At the same time, it did not differ from the active comparator (results not shown).
Table 5 SAR Study BILA 1003/RAE - Total Symptom Score - Area under the Curve (ITT Population)
| Placebo N=245 | Bilastine (20 mg) N=233 | P value1 | |
|---|---|---|---|
| Mean (SD) | 118.4 (62.7) | 98.4 (58.1) | <0.001 |
| 95% CI | 110.5, 126.3 | 90.9, 105.9 |
1 Tukey test
The individual component symptom scores that comprise the total symptom complex were also different for bilastine treated patients compared to placebo (Table 6).
Table 6 SAR Study BILA 1003/RAE - Summary of Key Secondary Results (ITT Population)
| Variable – Mean (SD) Change from Baseline to Day 14 | Placebo N=245 | Bilastine (20 mg) N=233 | Difference from Placebo | |||
|---|---|---|---|---|---|---|
| Estimate | 95% CI | |||||
| rTNSS | -2.3 (2.3) | -2.9 (2.2) | 0.67 | 0.27, 1.07 | ||
| rTNNSS | -1.3 (2.3) | -2.0 (2.1) | 0.70 | 0.30, 1.10 | ||
| TSS | -3.5 (4.2) | -4.9 (3.9) | 1.35 | 0.62, 2.08 | ||
| RQLQ Total Score | -1.3 (1.3) | -1.6 (1.2) | 0.3 | 0.07, 0.52 | ||
TSS – Total Symptom Score; rTNSS – reflective Nasal Symptoms Score; rTNNSS – reflective Non Nasal Symptom Score; RQLQ – Rhinoconjunctivitis Quality of Life Questionnaire
BILA 1704/RAE
Table 7 SAR Study BILA 1704/RAE - Total Symptom Score - Area under the Curve (ITT Population)
Placebo N=225 | Bilastine (20 mg) N=226 | P value1 | |
|---|---|---|---|
| Mean (SD) | 100.66 (51.71) | 76.49 (47.85) | <0.001 |
| 95% CI | 93.86, 107.45 | 70.21, 82.76 |
1 Tukey test
The individual component symptom scores that comprise the total symptom complex were also different for bilastine treated patients compared to placebo (Table 8).
Table 8 SAR Study BILA 1704/RAE - Summary of Key Secondary Results (ITT Population)
| Treatment Variable | Placebo N=225 | Bilastine (20 mg) N=226 | Difference from Placebo | ||
|---|---|---|---|---|---|
| Estimate | 95% CI | ||||
| rTNSS (mean change from baseline) | -2.0 (2.5) | -3.1 (2.3) | 1.15 | 0.70, 1.59 | |
| rTNNSS (mean change from baseline) | -0.9 (1.9) | -1.6 (1.9) | 0.73 | 0.38, 1.08 | |
| TSS (mean change from baseline) | -2.9 (4.1) | -4.8 (3.8) | 1.88 | 1.15, 2.61 | |
| TSS – Total Symptom Score; rTNSS – reflective Nasal Symptoms Score; rTNNSS – reflective Non Nasal Symptom Score; | |||||
Onset of action was evaluated in one environmental exposure unit study in allergic rhinitis patients with a single dose of bilastine. Bilastine was found to have an onset of action 1 hour after oral intake.
Efficacy in Chronic Spontaneous Urticaria
Study demographics and trial design
The efficacy of bilastine for the treatment of chronic spontaneous urticaria was evaluated in two multi-center, randomized, placebo-controlled, double-blind clinical trials of 4 weeks duration in adult patients 18 to 76 years of age with chronic spontaneous urticaria. The two trials included one 4-week dose-ranging trial (BILA 0601/UCI) and one 4-week single dose level efficacy trial (BILA 2006/UCI). These trials included 742 patients (229 males and 513 females). Most patients (>90%) were Caucasian and the mean age was 41.5. A total of 339 patients received bilastine (of these patients, 230 received bilastine 20 mg once daily) , and 237 received placebo.
Table 9 Summary of patient demographics for clinical trials in chronic spontaneous urticaria
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Gender M/F |
|---|---|---|---|---|---|
| BILA 0601/UCI | Double-blind, randomized, dose-ranging, placebo- controlled, parallel-group | Bilastine 10 mg Bilastine 20 mg Bilastine 30 mg Placebo Oral, once daily for 4 weeks | 53 58 56 53 ITT Total = 219 | 43 (18-76) | 15/33 13/25 9/28 8/21 PP Total* =152 |
BILA 2006/UCI (Zuberbier et al, 2010) | Double-blind, randomized, placebo- and levocetirizine- controlled parallel-group | Bilastine 20 mg **Levocetirizine 5 mg Placebo Oral, once daily for 4 weeks | 172 163 181 ITT Total = 516 | 40 (18-75) | 63/109 54/109 40/141 |
Efficacy was assessed based on the patients’ diary card on reflective urticaria symptoms - itching intensity, wheals number and maximum size of wheals - each scored on a 0-3 interval scale. The primary efficacy variable was the change from baseline in the mean of the morning (AM) and evening (PM) Total Symptom Score (TSS), defined as the sum of the itching intensity score, the wheals number score, and the maximum size of the wheals score, over the 28 days of the treatment period.
Study results BILA 0601/UCI
Table 10 CSU Study BILA 601/UCI – Total Symptom Score Change from Baseline at Day 28 (PP Population)
Placebo n=29 | Bilastine (20 mg) n=38 | P-value1 | ||||||
|---|---|---|---|---|---|---|---|---|
| Mean (SD) | -1.9 (2.8) | -4.1 (2.9) | 0.003 | |||||
| 95% CI | -2.92, -0.88 | -5.02, -3.18 | ||||||
1 T-test
The individual component symptom scores that comprise the total symptom complex were also different for bilastine treated patients compared to placebo (Table 11).
Table 11 CSU Study BILA 0601/UCI - Summary of Secondary Results (PP Population)
| Variable – Mean (SD) Change from Baseline to Day 28 | Placebo N=29 | Bilastine 20 mg N=38 | Difference from Placebo | |
|---|---|---|---|---|
| Estimate | 95% CI | |||
| IIS | -0.8 (1.1) | -1.5 (1.1) | 0.7 | 0.17, 1.23 |
| WNS | -0.6 (1.1) | -1.3 (1.1) | 0.7 | 0.17, 1.23 |
| MSWS | -0.6 (1.1) | -1.2 (1.2) | 0.6 | 0.04, 1.15 |
| Investigator’s CGI (median(range)) | 9 (1-15) | 3.5 (1-15) | --- | ---- |
IIS: Itching Intensity Score, WNS: Wheal Number Score, MSWS: Maximum Size of Wheal Score, CGI: Clinical Global Impression
BILA 2006/UCI
Table 12 CSU Study BILA 2006/UCI - Change from Baseline in the AM/PM TSS over the 28 Days of Treatment Period (ITT Population)
Placebo n=181 | Bilastine (20 mg) n=172 | P-value1 | |
|---|---|---|---|
| Mean (SD) | -2.99 (2.16) | -4.23 (2.1) | <0.001 |
| 95% CI | -3.67, -2.31 | -4.89, -3.57 |
1 Tukey test
Table 13 CSU Study BILA 2006/UCI - Summary of Secondary Results (ITT Population)
| Variable – Mean (SD) Change from Baseline to Day 28 | Placebo N=181 | Bilastine 20 mg N=172 | Difference from Placebo | |
|---|---|---|---|---|
| Estimate | 95% CI | |||
| IIS | -1.01 (0.78) | -1.48 (0.73) | 0.47 | 0.31, 0.63 |
| WNS | -1.00 (0.74) | -1.37 (0.73) | 0.37 | 0.22, 0.52 |
| MSWS | -0.97 (0.80) | -1.37 (0.83) | 0.40 | 0.23, 0.57 |
| Investigator’s CGI (median(range)) | 6 (1-13) | 5 (1-9) | --- | ---- |
|---|
IIS: Itching Intensity Score, WNS: Wheal Number Score, MSWS: Maximum Size of Wheal Score, CGI: Clinical Global Impression
The efficacy of bilastine has been studied in adults and adolescents. The proven efficacy in adults for chronic spontaneous urticaria can be extrapolated to adolescents, having demonstrated that the systemic exposure with 20 mg bilastine in adolescents from 12 to 17 years is equivalent to the exposure in adults with 20 mg bilastine.
14.3 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of Auro-Bilastine 20 mg tablets (Auro Pharma Inc.) with prBLEXTEN® 20 mg tablets (Aralez
Pharmaceuticals Canada Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from the 41 subjects that were included in the statistical analysis are presented in the following tables.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Bilastine (1 X 20 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 1349.4 1412.4 (30.8) | 1426.5 1472.9 (30.6) | 94.6 | 88.7 - 100.8 |
AUCI (ng•h/mL) | 1364.8 1427.1 (30.4) | 1441.6 1487.1 (30.3) | 94.7 | 88.8 - 100.9 |
Cmax (ng/mL) | 249.4 265.6 (34.4) | 257.1 273.1 (37.7) | 97.0 | 87.1 - 108.1 |
Tmax3 (h) | 1.0 (0.5 – 3.0) | 1.0 (0.5 – 5.0) | ||
T½4 (h) | 5.7 (60.6) | 6.2 (56.6) | ||
1Auro-Bilastine (bilastine) tablets, 20 mg (Auro Pharma Inc.).
2 PrBLEXTEN® (bilastine) tablets, 20 mg (Aralez Pharmaceuticals Canada Inc.).
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
15. NON-CLINICAL TOXICOLOGY
Single-Dose Toxicity
Bilastine has a low order of acute oral toxicity and there were no clinical signs or deaths after a single oral dose of 2000 mg/kg in rats and 5000 mg/kg in mice. After single i.v. dose administration, bilastine was lethal at ≥60 mg/kg in rats and at ≥30 mg/kg in mice. In both rats and mice, death occurred within 5 minutes of dosing and was preceded by signs such as tonic- clonic convulsions, prostration, and/or dyspnea. The lowest non-lethal dose was
45 mg/kg in rats and 20 mg/kg in mice. Plasma bilastine concentrations were determined after i.v. dosing in the rat; at 50 mg/kg, concentrations at the earliest sampling point (10 min after i.v. dosing) were >190 times the clinical Cmax at maximum recommended human dose (MRHD).
Repeat-Dose Toxicity
Repeat oral dose toxicity studies were performed in mice, rats, and dogs for up to 13, 26 and 52 weeks, respectively. Toxicity of bilastine administered i.v. daily for 4 weeks was evaluated in rats and dogs.
Oral bilastine administration of up to 2000 mg/kg/day in mice and rats and 800 mg/kg/day in dogs resulted in no signs in mice and transient clinical signs in rats and dogs (salivation in rats; vomiting, salivation, soft feces/diarrhea, and decreased activity in the dog). QTc was slightly increased in dogs at the end of 52 weeks of oral dosing at 800 mg/kg/day. Clinical pathology changes in rats and dogs were generally mild, occurred at high doses, and were reversible after 2 to 8 weeks without dosing. Liver and thyroid changes were noted in mice and rats and were considered adaptive responses. In the dog, at 800 mg/kg after dosing for 52 weeks, there was an increase in epididymal spermatozoa with abnormal morphology and one male had reduced spermatozoa motility. There were no histopathological changes in testes and prostate in the 52-week dog study.
After daily i.v. dosing for 4 weeks at doses up to 50 mg/kg/day in the rat, there were no clinical signs noted, but 4 out of 58 rats given 50 mg/kg/day were found dead. In the kidney at 50 mg/kg/day, there was minimal to slight proximal tubule hypertrophy in the cortico-medullary region of the kidney. All dogs survived 60 mg/kg/day i.v. for 4 weeks, there were dose related increased incidences of tremor and lip smacking post dose at all doses (≥30 mg/kg/day), and vomiting was seen during and after administration of 40 and 60 mg/kg/day. Increased severity of venous thrombosis at and around the injection sites was noted at 60 mg/kg/day. After i.v. dosing in the dog, there were no effects on cardiovascular parameters or changes in epididymal spermatozoa morphology and motility.
No Adverse Effect Levels (NOAELs) were determined for all findings in repeat oral and i.v. dose studies. The margin to clinical Cmax and AUC at the MRHD is at least 10 times and for most findings several hundred times.
Genotoxicity
Bilastine was not mutagenic in bacterial mutation assays at concentrations up to 2000 μg/plate or clastogenic in a human lymphocyte chromosome aberration assay at concentrations up to 500 μg/mL. In the in vivo mouse micronucleus test, single oral bilastine doses of 2000 mg/kg did not induce clastogenicity.
Carcinogenicity
In carcinogenicity studies in mice and rats, there were no bilastine related increases in tumor incidence at dose levels up to 2,000 mg/kg/day in mice and 1,200 mg/kg/day in rats administered in the diet for up to 104 weeks at which AUCs were >100 times higher than at the MRHD. In the rat carcinogenicity study, urolithiasis was noted in females at 1200 mg/kg/day. At the NOAEL of 700 mg/kg/day for this finding, AUCs were >200 times that of clinical values at MRHD.
Reproductive Toxicity
In rats, daily oral administration of bilastine prior to and during mating and early pregnancy had no effect on female and male fertility, epididymal sperm count, motility and morphology and early embryonic development at doses up to 1000 mg/kg/day. Bilastine administered daily by oral gavage to pregnant rats and rabbits during the period of major organogenesis did not result in maternal or embryofetal toxicity in the rat at doses up to 1000 mg/kg/day. At a maternally toxic dose in rabbits (400 mg/kg/day), findings consistent with delayed skeletal ossification in the fetuses were probably related to reduced food consumption by the does, with 110 mg/kg/day identified as a NOAEL. In a peri- and post-natal development study, bilastine was administered orally to pregnant rats (F0 generation) at 75, 275, and 1000 mg/kg/day from gestation day 6 to lactation day 21. There were no clinical signs in the treated females and no effects on mating or pregnancy duration and index, and all the females delivered, nursed, and cared for their offspring normally. At the high dose, there was a slight reduction in body weight and body weight gain during lactation and one female had 100% post implantation loss. There were no effects of bilastine treatment of the dams on pup development, sensory function, and motor development (F1 generation). The treatment of the dams had no effects on the offspring's reproductive capacity or their offspring (F2 generation). The NOAEL for the F0 generation was 275 mg/kg/day and the NOAEL for the offspring was 1000 mg/kg/day. The NOAELs for all reproductive endpoints in rats and rabbits were associated with AUCs >50 times higher than the clinical exposure at the MRHD.
17 SUPPORTING PRODUCT MONOGRAPHS
BLEXTEN (Tablets, 20 mg), Control No. 241318, Product Monograph, Aralez Pharmaceuticals Canada Inc. (August 10, 2021).