


Product Monograph - Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ...................................................................................................................... 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics ................................................................................................................... 4
2 CONTRAINDICATIONS ......................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................... 5
4 DOSAGE AND ADMINISTRATION ........................................................................................ 5
4.1 Dosing Considerations ............................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment .......................................................... 6
4.4 Administration .......................................................................................................... 7
4.5 Missed Dose .............................................................................................................. 8
5 OVERDOSAGE ..................................................................................................................... 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................................ 8
7 WARNINGS AND PRECAUTIONS .......................................................................................... 9
7.1 Special Populations ................................................................................................. 18
7.1.1 Pregnant Women ................................................................................................. 18
7.1.2 Breast-feeding ...................................................................................................... 19
7.1.3 Pediatrics ............................................................................................................. 19
7.1.4 Geriatrics .............................................................................................................. 19
8 ADVERSE REACTIONS ........................................................................................................ 19
8.1 Adverse Reaction Overview .................................................................................... 20
8.2 Clinical Trial Adverse Reactions ............................................................................... 21
8.2.1 Clinical Trial Adverse Reactions - Pediatrics ......................................................... 29
8.3 Less Common Clinical Trial Adverse Reactions ........................................................ 29
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .............................................................................................. 30
8.5 Post-Market Adverse Reactions .............................................................................. 31
9 DRUG INTERACTIONS ....................................................................................................... 32
9.2 Drug Interactions Overview .................................................................................... 32
9.3 Drug-Behavioural Interactions ................................................................................ 32
9.4 Drug-Drug Interactions ........................................................................................... 33
9.5 Drug-Food Interactions ........................................................................................... 35
9.6 Drug-Herb Interactions ........................................................................................... 36
9.7 Drug-Laboratory Test Interactions .......................................................................... 36
10 CLINICAL PHARMACOLOGY ............................................................................................. 36
10.1 Mechanism of Action ............................................................................................ 36
10.2 Pharmacodynamics ............................................................................................... 39
10.3 Pharmacokinetics .................................................................................................. 41
11 STORAGE, STABILITY AND DISPOSAL ............................................................................... 45
PART II: SCIENTIFICINFORMATION ...................................................................................... 46
13 PHARMACEUTICAL INFORMATION ................................................................................. 46
14 CLINICAL TRIALS ............................................................................................................ 47
14.1 Clinical Trials by Indication .................................................................................... 47
Sitagliptin in Combination with Metformin ................................................................... 47
Sitagliptin Add-on Combination Therapy ...................................................................... 49
14.2 Comparative Bioavailability Studies: ..................................................................... 55
15 MICROBIOLOGY .............................................................................................................. 57
16 NON-CLINICAL TOXICOLOGY ........................................................................................... 57
17 SUPPORTING PRODUCT MONOGRAPHS ......................................................................... 60
PATIENT MEDICATION INFORMATION ................................................................................ 61
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
- Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride (sitagliptin and metformin hydrochloride) are indicated for use as an adjunct to diet and exercise to improve glycemic control in adult patients with type 2 diabetes mellitus inadequately controlled on metformin or in patients already being treated with the combination of sitagliptin and metformin.
Add-on combination: Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride are indicated for use as a triple combination therapy in adult patients with type 2 diabetes mellitus to improve glycemic control, in combination with:
- i. sulfonylurea,
- ii. premixed or long/intermediate acting insulin
- iii. pioglitazone
when the existing dual therapy with metformin, along with diet and exercise, does not provide adequate glycemic control (see 14 CLINICAL TRIALS).
1.1 Pediatrics
- Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sitagliptin and metformin hydrochloride tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
- Geriatrics (≥65 years of age): Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be used with caution in geriatric patients. Sitagliptin and metformin are substantially excreted by the kidney. Because aging can be associated with reduced renal function, care should be taken in dose selection and should be based on careful and regular monitoring of renal function (see 4 DOSING and ADMINISTRATION,7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, and Special Populations).
2 CONTRAINDICATIONS
- Unstable and/or insulin-dependent (type 1) diabetes mellitus.
- Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma, history of ketoacidosis with or without coma.
In patients with a history of lactic acidosis, irrespective of precipitating factors (see 7 WARNINGS AND PRECAUTIONS).
In the presence of severe renal impairment [estimate glomerular filtration rate (eGFR)
- <30 mL/min/1.73 m2)], end-stage renal disease, in patients on dialysis or when renal function is not known (see 7 WARNINGS AND PRECAUTIONS).
- In excessive alcohol intake, acute or chronic.
- In patients suffering from severe hepatic dysfunction, since severe hepatic dysfunction has been associated with some cases of lactic acidosis, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should not be used in patients with clinical or laboratory evidence of hepatic disease.
- In cases of cardiovascular collapse and in disease states associated with hypoxemia such as cardiorespiratory insufficiency, which are often associated with hyperlactacidemia.
- During stress conditions, such as severe infections, trauma or surgery and the recovery phase thereafter.
- In patients suffering from severe dehydration or shock.
- Known hypersensitivity to sitagliptin, metformin or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS). For a complete listing, see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section.
- During pregnancy and breastfeeding (see 7 WARNINGS AND PRECAUTIONS, Special populations).
- During period around administration of iodinated contrast materials, because the use of such products may result in acute alteration of renal function (see 7 WARNINGS AND PRECAUTIONS).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Lactic Acidosis
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
|
|---|
Concomitant Use with Insulin or an Insulin Secretagogue (e.g., Sulfonylurea)
When Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is used as add-on therapy with insulin or an insulin secretagogue (e.g., sulfonylurea), a lower dose of insulin or the insulin secretagogue may be considered to reduce the risk of hypoglycemia (see 7 WARNINGS AND PRECAUTIONS and 8 ADVERSE REACTIONS).
Concomitant Use with Medication(s) that May Decrease Renal Function
Caution should be exercised when using concomitant medication(s) that may decrease renal function (like diuretics, particularly loop diuretics) or may interfere with the disposition of metformin, such as cationic drugs, that are eliminated by renal tubular secretion, due to the increased risk of developing lactic acidosis during co-administration (see 9 DRUG INTERACTIONS).
4.2 Recommended Dose and Dosage Adjustment
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is available in the following dosage strengths:
|
|---|
One Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride tablet should be taken orally twice a day with meals to reduce the risk of gastrointestinal side effects associated with metformin use. Tablets are to be swallowed whole.
In patients on metformin (alone or in combination with a sulfonylurea, pioglitazone, or insulin), the recommended total daily dose of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is 100 mg sitagliptin and the nearest therapeutically appropriate dose of metformin already being taken.
In patients already treated with sitagliptin and metformin, switching to Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride may be initiated at the dose of sitagliptin and metformin already being taken.
Renal Impairment: Renal function must be assessed prior to initiation of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride and periodically thereafter because there is a dosage adjustment based upon renal function. In patients with eGFR <60 mL/min/1.73m2, more intensive monitoring for glycemic biomarkers, renal biomarkers and signs and symptoms of renal dysfunction is recommended especially if the eGFR is less than 45 mL/min/1.73 m2 (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe renal impairment (eGFR <30 mL/min/1.73 m2), end stage renal disease or patients on dialysis (see 2 CONTRAINDICATIONS).
No dosage adjustment for Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is necessary in patients with mild (eGFR ≥60 mL/min/1.73 m2 to <90 mL/min/1.73 m2) to moderate renal impairment (eGFR ≥45 mL/min/1.73 m2 to <60 mL/min/1.73 m2).
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is not recommended in patients with an eGFR ≥30 mL/min/1.73 m2 and <45 mL/min/1.73 m2 because these patients require a lower dosage of sitagliptin than what is available in the fixed combination Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride product.
Discontinuation for iodinated contrast imaging procedures:
Discontinue Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR ≥30 to <60 mL/min/1.73 m2; in patients with a history of liver disease, alcoholism or heart failure; or in patients who will be administered intra-arterial iodinated contrast. Re-evaluate eGFR 48 hours after the imaging procedure; restart Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride if renal function is acceptable and found to be stable (see 7 WARNINGS AND PRECAUTIONS).
Hepatic Impairment: Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe hepatic impairment and should not be used in patients with clinical or laboratory evidence of hepatic disease (see 2 CONTRAINDICATIONS). Metformin use in patients with impaired hepatic function has been associated with some cases of lactic acidosis (see 7 WARNINGS AND PRECAUTIONS).
Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use.
Geriatrics (≥65 years of age): Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be used with caution in patients 65 years and older. Regular assessment of renal function is necessary. Metformin and sitagliptin are excreted by the kidneys, and elderly patients are more likely to have decreased renal function associated with aging and be at risk of developing lactic acidosis (see 7 WARNINGS AND PRECAUTION, Special Populations).
4.4 Administration
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be taken orally with meals.
4.5 Missed Dose
If a dose of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is missed, it should be taken as soon as the patient remembers. If he/she does not remember until it is time for the next dose, the missed dose should be skipped and returned to the regular schedule. A double dose of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should not be taken at the same time.
5 OVERDOSAGE
Sitagliptin
In the event of an overdose, it is reasonable to employ the usual supportive measures, e.g., remove unabsorbed material from the gastrointestinal tract, employ clinical monitoring (including obtaining an electrocardiogram), and institute supportive therapy if required.
Sitagliptin is modestly dialyzable. In clinical studies, approximately 13.5% of the dose was removed over a 3- to 4-hour hemodialysis session. Prolonged hemodialysis may be considered if clinically appropriate. It is not known if sitagliptin is dialyzable by peritoneal dialysis.
Metformin hydrochloride
Available information concerning treatment of a massive over dosage of metformin hydrochloride is very limited. It would be expected that adverse reactions of a more intense character including epigastric discomfort, nausea and vomiting followed by diarrhea, drowsiness, weakness, dizziness, malaise and headache might be seen. Should those symptoms persist, lactic acidosis should be excluded. The drug should be discontinued and proper supportive therapy instituted.
Overdose of metformin hydrochloride has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin hydrochloride has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases (see 7 WARNINGS AND PRECAUTIONS). Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin over dosage is suspected.
Pancreatitis may occur in the context of a metformin overdose (see 7 WARNINGS AND
PRECAUTIONS).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets: sitagliptin (as sitagliptin Hydrochloride monohydrate) / metformin hydrochloride 50 mg§/500 mg 50 mg§/850 mg 50 mg§/1000 mg | Cellulose Microcrystalline, Croscarmellose Sodium, Ferrosoferric oxide, Iron oxide Red NF, Iron oxide Yellow NF, macrogol, Poly vinyl alcohol, Povidone, Sodium Laurilsulfate, Sodium stearyl Fumarate, Talc and Titanium dioxide. |
§ 56.685 mg of sitagliptin hydrochloride monohydrate equivalent to 50 mg sitagliptin.
Description & Packing:
Sitagliptin and Metformin Hydrochloride Tablets 50 mg/500 mg:
Light pink, approximately 17.30 × 8.40 mm capsules shaped, biconvex, film coated tablets, debossed with “SL” on one side and “500” on the other side. They are supplied in bottles of 30, 60, 100, 180, 500 and 1000 tablets, and blister packs of 90 tablets (9 blister cards of 10 tablets).
Sitagliptin and Metformin Hydrochloride Tablets 50 mg/850 mg:
Light pink, approximately 20.00 × 9.70 mm capsules shaped, biconvex, film coated tablets, debossed with “SL” on one side and “850” on the other side. They are supplied in bottles of 30, 60, 100 and 500 tablets, and blister packs of 72 tablets (9 blister cards of 8 tablets).
Sitagliptin and Metformin Hydrochloride Tablets 50 mg/1000 mg:
Red, approximately 21.30 × 10.40 mm capsules shaped, biconvex, film coated tablets, debossed with “SL” on one side and “1000” on the other side. They are supplied in bottles of 30, 60, 100 and 500 tablets, and blister packs of 72 tablets (9 blister cards of 8 tablets).
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should not be used in patients with type 1 diabetes or for the treatment of diabetic ketoacidosis.
Cardiovascular
Hypoxic States:
Metformin hydrochloride
Cardiovascular collapse (shock) from whatever cause (e.g., acute congestive heart failure, acute myocardial infarction and other conditions characterized by hypoxemia) have been associated with lactic acidosis and may also cause prerenal azotemia (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism). When such events occur in patients on Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride therapy, the drug should be promptly discontinued.
Driving and Operating Machinery
Patients should be warned about driving or operating a vehicle or potentially dangerous machinery under conditions where a risk of hypoglycemia is present (see 7 WARNINGS AND PRECAUTIONS). When Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is used in combination with a sulfonylurea or in combination with insulin patients should be advised to take precautions to avoid hypoglycaemia while driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism Hypoglycemia:
Sitagliptin
When sitagliptin and metformin were used in combination with a sulfonylurea or in combination with insulin, the incidence of hypoglycemia was increased over that of placebo and metformin used in combination with a sulfonylurea or in combination with insulin (see 8 ADVERSE REACTIONS). To reduce the risk of hypoglycemia associated with these regimens, a lower dose of sulfonylurea or insulin maybe considered (see 4 DOSAGE AND ADMINISTRATION).
Metformin hydrochloride
Hypoglycemia does not occur in patients receiving metformin alone under usual circumstances of use, but could occur when caloric intake is deficient, when strenuous exercise is not compensated by caloric supplementation, or during concomitant use with other glucose-lowering agents(such as sulfonylureas and insulin) or ethanol. Elderly, debilitated, or malnourished patients and those with adrenal or pituitary insufficiency or alcohol intoxication are particularly susceptible to hypoglycemic effects. Hypoglycemia may be difficult to recognize in the elderly, and in people who are taking β-adrenergic blocking drugs.
Hypothyroidism:
Metformin hydrochloride
Metformin induces a reduction in thyrotropin (thyroid stimulating hormone (TSH) levels in patients with treated or untreated hypothyroidism (see 8 ADVERSE REACTIONS). Regular monitoring of TSH levels is recommended in patients with hypothyroidism (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Studies have shown that metformin reduces plasma TSH levels, often to subnormal levels, when it is administered to patients with untreated hypothyroidism or to hypothyroid patients effectively treated with levothyroxine. The metformin-induced reduction of plasma TSH levels is not observed when metformin is administered to patients with normal thyroid function.
Metformin has been suggested to enhance the inhibitory modulation of thyroid hormones on TSH secretion.
Levothyroxine can reduce the hypoglycemic effect of metformin. Careful monitoring of blood glucose levels is recommended in patients with hypothyroidism treated with levothyroxine, especially when thyroid hormone therapy is initiated, changed, or stopped (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 9 DRUG INTERACTIONS).
Lactic Acidosis:
Metformin hydrochloride
Lactic acidosis is a rare, but serious, metabolic complication that can occur due to metformin accumulation during treatment with Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride; when it occurs, it is fatal in approximately 50% of cases. Lactic acidosis may also occur in association with a number of pathophysiologic conditions, including diabetes mellitus, and whenever there is significant tissue hypoperfusion and hypoxemia. Lactic acidosis is characterized by elevated blood lactate levels (>5 mmol/L), decreased blood pH, electrolyte disturbances with an increased anion gap, and an increased lactate/pyruvate ratio. When metformin is implicated as the cause of lactic acidosis, metformin plasma levels >5 mcg/mL are generally found.
The reported incidence of lactic acidosis in patients receiving metformin hydrochloride is very low (approximately 0.03 cases/1000 patient-years, with approximately 0.015 fatal cases/1000 patient-years). Reported cases have occurred primarily in diabetic patients with significant renal impairment, including both intrinsic renal disease and renal hypoperfusion, often in the setting of multiple concomitant medical/surgical problems and multiple concomitant medications (see 4 DOSAGE AND ADMINISTRATION).
Patients with congestive heart failure requiring pharmacologic management, in particular those with unstable or acute congestive heart failure who are at risk of hypoperfusion and hypoxemia, are at increased risk of lactic acidosis. In particular, treatment of the elderly should be accompanied by careful monitoring of renal function. The risk of lactic acidosis increases with the degree of renal dysfunction and the patient’s age (see 7 WARNINGS AND PRECAUTIONS, Special Populations). The risk of lactic acidosis may, therefore, be significantly decreased by regular monitoring of renal function in patients taking metformin and by use of the minimum effective dose of metformin.
In addition, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be promptly withheld in the presence of any condition associated with hypoxemia, dehydration, or sepsis. Because impaired hepatic function may significantly limit the ability to clear lactate, metformin should generally be avoided in patients with clinical or laboratory evidence of hepatic disease.
Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, since alcohol potentiates the effects of metformin hydrochloride on lactate metabolism. In addition, Auro-Sitagliptin
Hydrochloride and Metformin Hydrochloride should be temporarily discontinued prior to any intravascular radiocontrast study and for any surgical procedure.
The onset of lactic acidosis often is subtle, and accompanied only by nonspecific symptoms such as malaise, myalgia, respiratory distress, increasing somnolence, and nonspecific abdominal distress. There may be associated hypothermia, hypotension, and resistant bradyarrhythmias with more marked acidosis. The patient and the patient’s physician must be aware of the possible importance of such symptoms and the patient should be instructed to notify the physician immediately if they occur. Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be withdrawn until the situation is clarified. Serum electrolytes, ketones, blood glucose, and if indicated, blood pH, lactate levels, and even blood metformin levels may be useful. Once a patient is stabilized on any dose level of metformin, gastrointestinal symptoms, which are common during initiation of therapy, are unlikely to be drug related. Later occurrence of gastrointestinal symptoms could be due to lactic acidosis or other serious disease.
Levels of fasting venous plasma lactate above the upper limit of normal but less than 5 mmol/L in patients taking metformin do not necessarily indicate impending lactic acidosis and may be explainable by other mechanisms, such as poorly controlled diabetes or obesity, vigorous physical activity, or technical problems in sample handling.
Lactic acidosis should be suspected in any diabetic patient with metabolic acidosis lacking evidence of ketoacidosis (ketonuria and ketonemia).
Lactic acidosis is a medical emergency that must be treated in a hospital setting. In a patient with lactic acidosis who is taking Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, the drug should be discontinued immediately and general supportive measures promptly instituted. Because metformin hydrochloride is dialyzable (with a clearance of up to 170 mL/min under good hemodynamic conditions), prompt hemodialysis is recommended to correct the acidosis and remove the accumulated metformin (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Hepatic/Biliary/Pancreatic and Renal).
Physicians should instruct their patients to recognize the symptoms which could be a signal of the onset of lactic acidosis. If acidosis of any kind develops, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be discontinued immediately and the patient should be immediately hospitalized.
Change in Clinical Status of Previously Controlled Diabetes Patients:
Metformin hydrochloride
A diabetic patient previously well controlled on Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride who develops laboratory abnormalities or clinical illness (especially vague and poorly defined illness) should be evaluated promptly for evidence of ketoacidosis or lactic acidosis. Evaluation should include serum electrolytes and ketones, blood glucose and, if indicated, blood pH, lactate, pyruvate and metformin levels. If acidosis of either form occurs, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride must be stopped immediately and appropriate corrective measures initiated.
Loss of Control of Blood Glucose:
The effectiveness of oral antidiabetic drugs in lowering blood glucose to a targeted level decreases in many patients over a period of time. This phenomenon, which may be due to progression of the underlying disease or to diminished responsiveness to the drug, is known as secondary failure, to distinguish it from primary failure in which the drug is ineffective during initial therapy. Should secondary failure occur with Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, therapeutic alternatives should be considered.
Metformin hydrochloride
When a patient stabilized on any diabetic regimen is exposed to stress such as fever, trauma, infection, or surgery, a temporary loss of glycemic control may occur. At such times, it may be necessary to withhold Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride and temporarily administer insulin. Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride may be reinstituted after the acute episode is resolved.
Vitamin B12 Levels:
Metformin hydrochloride
Impairment of vitamin B12 absorption has been reported in some patients treated with metformin. Therefore, measurements of serum vitamin B12 are advisable at least every one to two years in patients on long-term treatment with Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride.
A decrease to subnormal levels of previously normal serum vitamin B12 levels, without clinical manifestations, is observed in approximately 7% of patients receiving metformin in controlled clinical trials of 28 weeks duration. Such decrease, possibly due to interference with B12 absorption from the B12-intrinsic factor complex, is, however, very rarely associated with anemia and appears to be rapidly reversible with discontinuation of metformin or vitamin B12 supplementation. Measurement of hematologic parameters on an annual basis is advised in patients on Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride and any apparent abnormalities should be appropriately investigated and managed (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests). Certain individuals (those with inadequate vitamin B12 or calcium intake or absorption) appear to be predisposed to developing subnormal vitamin B12 levels.
Long-term treatment with metformin has been associated with a decrease in serum vitamin B12 levels which may cause peripheral neuropathy. Serious cases of peripheral neuropathy have been reported with metformin treatment, one of the components of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, in the context of vitamin B12 deficiency (see 8
ADVERSE REACTIONS). Monitoring of serum vitamin B12 levels is recommended (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Hematologic
Metformin hydrochloride
Serious cases of metformin-induced hemolytic anemia, some with fatal outcome, have been reported (see 8 ADVERSE REACTIONS). Two mechanisms were described for the metformin-induced immune hemolytic anemia; formation of an antibody against the erythrocyte-metformin complex and autoantibody formation. Monitoring of hematologic parameters is recommended (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests).
Hepatic/Biliary/Pancreatic
Hepatic: Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe hepatic dysfunction and should not be used in patients with clinical or laboratory evidence of hepatic disease (see 2 CONTRAINDICATIONS).
Sitagliptin
There are limited clinical experiences in patients with moderate hepatic impairment and no clinical experience in patients with severe hepatic impairment. Use in patients with severe hepatic impairment is not recommended (see 10 CLINICAL PHARMACOLOGY).
Metformin hydrochloride
Impaired hepatic function has been associated with some cases of lactic acidosis.
Pancreatitis:
Sitagliptin
There have been reports of acute pancreatitis, including fatal and non-fatal hemorrhagic or necrotizing pancreatitis, in patients taking sitagliptin, one of the components of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride. Ina long-term cardiovascular outcomes trial (see 8 ADVERSE REACTIONS and CLINICAL TRIALS), there were two adjudication-confirmed deaths due to acute pancreatitis in sitagliptin patients compared to none in the placebo group. After initiation of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, patients should be observed carefully for signs and symptoms of pancreatitis. If pancreatitis is suspected, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should promptly be discontinued and appropriate management should be initiated. Risk factors for pancreatitis include a history of: pancreatitis, gallstones, alcoholism, or hypertriglyceridemia.
Metformin hydrochloride
Serious cases of pancreatitis have been reported in patients receiving metformin (see 8 ADVERSE REACTIONS). The reported pancreatitis cases occurred either in the context of an acute metformin overdose (see 5 OVERDOSAGE) or in patients receiving therapeutic doses of metformin with concurrent renal failure and/or lactic acidosis, indicating metformin accumulation.
Immune
Hypersensitivity Reactions:
Sitagliptin
There have been post-marketing reports of serious hypersensitivity reactions in patients treated with sitagliptin, one of the components of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride. These reactions include anaphylaxis, angioedema, and exfoliative skin conditions including Stevens-Johnson syndrome. Onset of these reactions occurred within the first 3 months after initiation of treatment with sitagliptin, with some reports occurring after the first dose. If a hypersensitivity reaction is suspected, discontinue Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, assess for other potential causes for the event, and institute alternative treatment for diabetes (see 2 CONTRAINDICATIONS and 8 ADVERSE REACTIONS).
Immunocompromised Patients:
Sitagliptin
A dose-related mean decrease in absolute lymphocyte count was observed with other dipeptidyl peptidase 4 (DPP-4) inhibitors. When clinically indicated, such as in settings of unusual or prolonged infection, lymphocyte count should be measured. The effect of sitagliptin, a component of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, on lymphocyte counts in patients with lymphocyte abnormalities (e.g. human immunodeficiency virus) is unknown.
Immunocompromised patients, such as patients who have undergone organ transplantation or patients diagnosed with human immunodeficiency syndrome have not been studied in the sitagliptin clinical program. Therefore, the efficacy and safety profile of sitagliptin in these patients has not been established.
Monitoring and Laboratory Tests
Blood Glucose and HbA1c: Response to Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride treatment should be monitored by periodic measurements of blood glucose and HbA1c levels.
Hematology: Initial and periodic monitoring of hematologic parameters (e.g., hemoglobin/hematocrit and red blood cell indices) should be performed, regularly. While megaloblastic anemia has rarely been seen with metformin therapy, if this is suspected, vitamin B12 deficiency should be excluded. Periodic measurements of serum vitamin B12 levels should be performed in patients on long-term treatment with Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, especially in patients with anemia or neuropathy (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
A close monitoring of the International Normalized Ratio (INR) is recommended in patients concurrently administering metformin and phenprocoumon or other antivitamin K anticoagulants (see 9 DRUG INTERACTIONS).
Hypothyroidism: Regular monitoring of thyroid-stimulating hormone (TSH) levels is recommended in patients with hypothyroidism.
For hypothyroid patients treated with levothyroxine, careful monitoring of blood glucose levels is recommended, especially when thyroid hormone therapy is initiated, changed, or stopped (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, and 9 DRUG INTERACTIONS).
Renal Function: Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with an estimated glomerular rate (eGFR) <30 mL/min/1.73 m2 (see 2 CONTRAINDICATIONS). Renal function must be assessed prior to initiation of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride and periodically thereafter, with more frequent monitoring in patients whose eGFR decreases to less than 60 mL/min/1.73 m2 (see 4 DOSAGE AND ADMINISTRATION).
Monitoring of renal function is recommended prior to and following initiation of any concomitant drug which might have an impact on renal function (see 9 DRUG INTERACTIONS).
Neurologic
Metformin hydrochloride
Serious cases of metformin-induced encephalopathy have been reported (see 8 ADVERSE REACTIONS). Some of these cases were reported without association with lactic acidosis, hypoglycemia, or renal impairment.
Peri-Operative Considerations
Metformin hydrochloride
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride therapy should be temporarily suspended for any surgical procedure (except minor procedures not associated with restricted intake of food and fluids). Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be discontinued 2 days before surgical intervention and should not be restarted until the patient’s oral intake has resumed and renal function has been evaluated as acceptable and found to be stable (see 4 DOSAGE AND ADMINISTRATION).
Renal
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe renal impairment (eGFR <30 mL/min/1.73 m2) (see 2 CONTRAINDICATIONS).
Before initiation of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride therapy and regularly thereafter, renal function must be assessed. In patients with eGFR less than 60 mL/min/1.73m2, more intensive monitoring for glycemic and renal biomarkers and signs and symptoms of renal dysfunction is recommended, especially if the eGFR is less than 45 mL/min/1.73 m2 (see 7 WARNINGS AND PRECAUTIONS, Monitoring and Laboratory Tests and 4 DOSAGE AND ADMINISTRATION).
In patients in whom development of renal dysfunction is anticipated, renal function should be assessed more frequently and Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride discontinued if evidence of renal impairment is present.
Special caution should be exercised in situations where renal function may become impaired, for example in the elderly, in the case of dehydration when initiating antihypertensive therapy or diuretic therapy or when starting therapy with a non-steroidal anti-inflammatory drug (NSAID). Therefore, consider more frequent monitoring of patients.
Sitagliptin
Sitagliptin is renally excreted. Renal adverse events, including acute renal failure, have been observed during clinical trials and post-marketing use of sitagliptin, a component of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, in patients with and without known risk factors (see 8 ADVERSE REACTIONS).
Metformin hydrochloride
Metformin is known to be substantially excreted by the kidney, and the risk of metformin accumulation and lactic acidosis increases with the degree of impairment of renal function.
Use of concomitant medications that may affect renal function or metformin disposition:
Concomitant medication(s) that may affect renal function or result in significant hemodynamic change or may interfere with the disposition of metformin, such as cationic drugs, that are eliminated by renal tubular secretion (see 9 DRUG INTERACTIONS) should be used with caution.
The concomitant use of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride with these specific drugs may increase the risk of metformin-associated lactic acidosis and therefore, consider more frequent monitoring of patients.
Radiologic studies involving the use of intravascular iodinated contrast materials (for example, intravenous urogram, intravenous cholangiography, angiography, and computed tomography (CT) scans with intravascular contrast materials): Intravascular contrast studies with iodinated materials can lead to acute alteration of renal function and have been associated with lactic acidosis in patients receiving metformin (see 2 CONTRAINDICATIONS). Therefore, inpatients with an eGFR ≥ 30 to < 60 mL/min/1.73 m2, in patients with a history of hepatic impairment, alcoholism, or heart failure, or in patients who will be administered intra-arterial iodinated contrast, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be discontinued at the time of or prior to the procedure, and withheld for 48 hours subsequent to the procedure and reinstituted only after renal function has been re-evaluated and found to be acceptable and stable (see 4 DOSAGE AND ADMINISTRATION).
Reproductive Health: Female and Male Potential
See 2 CONTRAINDICATIONS and 7.1.1 SPECIAL POPULATIONS, Pregnant Women
Skin
Sitagliptin
With other members of this class, DPP-4 inhibitors, ulcerative and necrotic skin lesions have been reported in monkeys in non-clinical toxicology studies. There is limited experience in patients with diabetic skin complications with sitagliptin, a component of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride. In keeping with routine care of the diabetic patient, monitoring for skin disorders is recommended.
Bullous Pemphigoid: Post-marketing cases of bullous pemphigoid requiring hospitalization have been reported with the use of DPP-4 inhibitors, including sitagliptin, a component of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride. In reported cases, patients typically recovered with topical or systemic immunosuppressive treatment and discontinuation of the DPP-4 inhibitor. Tell patients to report development of blisters or erosions while receiving Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride. If bullous pemphigoid is suspected, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be discontinued and referral to a dermatologist should be considered for diagnosis and appropriate treatment.
7.1 Special Populations
7.1.1 Pregnant Women
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in pregnancy (see 2 CONTRAINDICATIONS). There are no adequate and well-controlled studies in pregnant women with sitagliptin hydrochloride and metformin hydrochloride or their individual components; therefore, the safety of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride in pregnant women is not known. When pregnancy is detected, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be discontinued.
The extent of exposure in pregnancy during clinical trials: Very limited
Sitagliptin
There are very limited data for the use of sitagliptin in pregnant women in clinical studies, including no adequate and well-controlled studies in this population; therefore, the safety of sitagliptin in pregnant women is not known.
Metformin hydrochloride
Metformin was not teratogenic in rats and rabbits at doses up to 600 mg/kg/day, or about two and six times the maximum recommended human daily dose on a body surface area basis. Determination of fetal concentrations demonstrated a partial placental barrier to metformin. Because animal reproduction studies are not always predictive of human response, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated during pregnancy (see 2 CONTRAINDICATIONS).
7.1.2 Breast-feeding
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated during breast-feeding (see 2 CONTRAINDICATIONS). No studies in lactating animals have been conducted with the combined components of sitagliptin and metformin hydrochloride tablets. Both sitagliptin and metformin are present in the milk of lactating rats. Metformin hydrochloride is also excreted into human breast milk in very small amounts but it is unknown if sitagliptin is excreted in human milk. Therefore, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should not be used by a woman during breastfeeding.
7.1.3 Pediatrics
Pediatrics (<18 years of age):
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of sitagliptin and metformin hydrochloride in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Because sitagliptin and metformin are substantially excreted by the kidney and because aging can be associated with reduced renal function, Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride should be used with caution as age increases. Care should be taken in dose selection and should be based on careful and regular monitoring of renal function (see 7 WARNINGS AND PRECAUTIONS, Renal, and 4 DOSAGE AND ADMINISTRATION).
Sitagliptin
In clinical studies, no overall differences in safety or effectiveness were observed between subjects 65 years and over and younger subjects. While this and other reported clinical experience have not identified differences in responses between the geriatric and younger patients, greater sensitivity of some older individuals cannot be ruled out. Renal function should be assessed prior to initiating dosing and periodically thereafter in geriatric patients (see 4 DOSAGE AND ADMINISTRATION and 10 CLINICAL PHARMACOLOGY).
Metformin hydrochloride
Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and younger patients. The risk of metformin-associated lactic acidosis increases with the patient’s age because elderly patients have a greater likelihood of having hepatic, renal, or cardiac impairment than younger patients. Assess renal function more frequently in elderly patients.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Sitagliptin
Sitagliptin was generally well tolerated in controlled clinical studies as monotherapy and as part of a combination therapy with metformin or combination therapy with metformin and a sulfonylurea or combination therapy with metformin, insulin and pioglitazone.
The incidences of serious adverse reactions and discontinuation of therapy due to clinical adverse reactions were generally similar to placebo. The most frequent adverse events in trials of sitagliptin as monotherapy (placebo-controlled) and as add-on combination therapy with metformin (reported regardless of causality and more common with sitagliptin than other treatments) was nasopharyngitis. The most frequent adverse reaction with sitagliptin as add-on combination therapy with metformin and a sulfonylurea agent or with metformin and insulin was hypoglycemia.
Metformin hydrochloride
The adverse events most commonly associated with metformin (sitagliptin/metformin) are diarrhea, nausea, and upset stomach. Similar adverse reactions were seen in patients treated with modified-release metformin products. Lactic acidosis is a rare, but serious side effect. Lactic acidosis is fatal in approximately 50% of cases.
Lactic Acidosis: very rare (<1/10, 000 and isolated reports) (see 7 WARNINGS AND PRECAUTIONS and 5 OVERDOSAGE).
Gastrointestinal Reactions: very common (>1/10): Gastrointestinal symptoms (diarrhea, nausea, vomiting, abdominal bloating, flatulence, and anorexia) are the most common reactions to metformin and are approximately 30% more frequent in patients on metformin monotherapy than in placebo-treated patients, particularly during initiation of metformin therapy. These symptoms are generally transient and resolve spontaneously during continued treatment. Occasionally, temporary dose reduction may be useful.
Because gastrointestinal symptoms during therapy initiation appear to be dose-related, they may be decreased by gradual dose escalation and by having patients take metformin (metformin hydrochloride) with meals (see 4 DOSAGE AND ADMINISTRATION).
Because significant diarrhea and/or vomiting can cause dehydration and prerenal azotemia, metformin should be temporarily discontinued, under such circumstances.
For patients who have been stabilized on metformin, nonspecific gastrointestinal symptoms should not be attributed to therapy unless intercurrent illness or lactic acidosis have been excluded.
Special Senses: common (≥1/100): During initiation of metformin therapy complaints of taste disturbance are common, i.e. metallic taste.
Dermatologic Reactions: very rare (<1/10,000 and isolated reports): The incidence of rash/dermatitis in controlled clinical trials was comparable to placebo for metformin monotherapy and to sulfonylurea for metformin /sulfonylurea therapy. Reports of skin reactions such as erythema, pruritus, and urticaria are very rare.
Hematologic: Decrease of vitamin B12 absorption with decrease of serum levels during long-term use of metformin is rare (≥1/10,000 and <1/1,000). Consideration of such etiology is recommended if a patient presents with megaloblastic anemia.
Hepatic: very rare (<1/10,000 and isolated reports): Liver function tests abnormalities or hepatitis resolving upon metformin discontinuation has been documented in isolated reports.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Combination Therapy – Sitagliptin Add-on to Metformin:
In a 24-week placebo-controlled clinical study of patients receiving sitagliptin (100 mg daily) as add-on combination therapy with metformin, the incidence of adverse events, reported regardless of causality assessment, in ≥1% of patients are shown in Table 2.
Table 2 – Adverse Events ≥1% in Any Treatment Group (regardless of causality) Reported in Patients in a 24-week Placebo-Controlled, Double-Blind Clinical Trial of Sitagliptin in Add-on Combination Use with Metformin
| Number of patients (%) | |||||
|---|---|---|---|---|---|
| Body system/Organ class Adverse event | Sitagliptin 100 mg + Metformin n=464 | Placebo + Metformin n=237 | |||
| Ear and labyrinth disorders | |||||
| Vertigo | 5 (1.1) | 4 (1.7) | |||
| Eye disorders | |||||
| Vision blurred | 1 (0.2) | 3 (1.3) | |||
| Gastrointestinal disorders | |||||
| Abdominal pain | 2 (0.4) | 6 (2.5) | |||
| Abdominal pain upper | 6 (1.3) | 2 (0.8) | |||
| Constipation | 5 (1.1) | 1 (0.4) | |||
| Diarrhea | 11 (2.4) | 6 (2.5) | |||
| Nausea | 6 (1.3) | 2 (0.8) | |||
| Vomiting | 5 (1.1) | 2 (0.8) | |||
| General disorders and administration site conditions | |||||
| Fatigue | 2 (0.4) | 4 (1.7) | |||
| Edema peripheral | 4 (0.9) | 3 (1.3) | |||
| Infections and infestations | ||
|---|---|---|
| Bronchitis | 12 (2.6) | 6 (2.5) |
| Bronchitis acute | 2 (0.4) | 3 (1.3) |
| Gastroenteritis | 4 (0.9) | 5 (2.1) |
| Influenza | 19 (4.1) | 12 (5.1) |
| Nasopharyngitis | 19 (4.1) | 7 (3.0) |
| Pharyngitis | 6 (1.3) | 1 (0.4) |
| Pneumonia | 5 (1.1) | 0 (0.0) |
| Sinusitis | 7 (1.5) | 2 (0.8) |
| Tooth infection | 5 (1.1) | 2 (0.8) |
| Upper respiratory tract infection | 34 (7.3) | 22 (9.3) |
| Urinary tract infection | 9 (1.9) | 2 (0.8) |
| Injury, poisoning and procedural complications | ||
| Contusion | 5 (1.1) | 1 (0.4) |
| Investigations | ||
| Blood glucose increased | 3 (0.6) | 6 (2.5) |
| Metabolism and nutrition disorders | ||
| Hyperglycemia | 2 (0.4) | 7 (3.0) |
| Hypoglycemia | 6 (1.3) | 5 (2.1) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 14 (3.0) | 1 (0.4) |
| Back pain | 15 (3.2) | 6 (2.5) |
| Muscle spasm | 1 (0.2) | 3 (1.3) |
| Myalgia | 1 (0.2) | 3 (1.3) |
| Pain in extremity | 5 (1.1) | 4 (1.7) |
| Shoulder pain | 3 (0.6) | 3 (1.3) |
| Nervous system disorders | ||
| Dizziness | 7 (1.5) | 2 (0.8) |
| Headache | 12 (2.6) | 7 (3.0) |
| Sciatica | 1 (0.2) | 3 (1.3) |
| Sinus headache | 0 (0.0) | 3 (1.3) |
| Psychiatric disorders | ||
| Insomnia | 5 (1.1) | 3 (1.3) |
| Renal and urinary disorders | ||
| Nephrolithiasis | 3 (0.6) | 3 (1.3) |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 14 (3.0) | 4 (1.7) |
| Vascular disorders | ||
| Hypertension | 7 (1.5) | 6 (2.5) |
Nausea was the only drug-related adverse reaction reported by the investigator that occurred with an incidence ≥1% in patients receiving sitagliptin (1.1%) and greater than in patients receiving placebo (0.4%).
In pooled studies of up to one year duration which compared sitagliptin added to metformin or a sulfonylurea agent (glipizide) added to metformin, adverse events, reported regardless of causality assessment, in ≥1% of patients are shown in Table 3.
Table 3 – Adverse Events ≥1% in Any Treatment Group (regardless of causality) Reported in Patients from Double-Blind Clinical Trials of Sitagliptin in Add-on Combination Use with Metformin in Studies Up to One Year Compared to a Sulfonylurea Agent (Glipizide)
| Number of patients (%) | |||||||
|---|---|---|---|---|---|---|---|
| Body system/Organ class Adverse event | Sitagliptin 100 mg + Metformin n=979 | Glipizide + Metformin n=748 | |||||
| Gastrointestinal disorders | |||||||
| Abdominal pain | 10 (1.0) | 6 (0.8) | |||||
| Abdominal pain upper | 13 (1.3) | 7 (0.9) | |||||
| Constipation | 17 (1.7) | 13 (1.7) | |||||
| Diarrhea | 42 (4.3) | 36 (4.8) | |||||
| Dyspepsia | 14 (1.4) | 12 (1.6) | |||||
| Nausea | 19 (1.9) | 16 (2.1) | |||||
| Toothache | 2 (0.2) | 13 (1.7) | |||||
| Vomiting | 11 (1.1) | 9 (1.2) | |||||
| General disorders and administration site conditions | |||||||
| Fatigue | 20 (2.0) | 8 (1.1) | |||||
| Non-cardiac chest pain | 10 (1.0) | 6 (0.8) | |||||
| Edema peripheral | 16 (1.6) | 14 (1.9) | |||||
| Infections and infestations | |||||||
| Bronchitis | 27 (2.8) | 22 (2.9) | |||||
| Cellulitis | 7 (0.7) | 10 (1.3) | |||||
| Gastroenteritis | 19 (1.9) | 13 (1.7) | |||||
| Gastroenteritis viral | 8 (0.8) | 9 (1.2) | |||||
| Herpes zoster | 4 (0.4) | 8 (1.1) | |||||
| Influenza | 35 (3.6) | 32 (4.3) | |||||
| Nasopharyngitis | 75 (7.7) | 49 (6.6) | |||||
| Sinusitis | 20 (2.0) | 12 (1.6) | |||||
| Upper respiratory tract infection | 78 (8.0) | 70 (9.4) | |||||
| Urinary tract infection | 41 (4.2) | 21 (2.8) | |||||
| Investigations | |||||||
| Blood glucose decreased | 5 (0.5) | 16 (2.1) | |||||
| Blood glucose increased | 13 (1.3) | 5 (0.7) | |||||
| Weight increased | 1 (0.1) | 8 (1.1) | |||||
| Metabolism and nutrition disorders | |||||||
| Hyperglycemia | 10 (1.0) | 6 (0.8) | |||||
| Hypoglycemia | 32 (3.3) | 217 (29.0) | |||||
| Musculoskeletal and connective tissue disorders | |||||||
| Arthralgia | 34 (3.5) | 29 (3.9) | |||||
| Back pain | 39 (4.0) | 32 (4.3) | |||||
| Muscle spasms | 9 (0.9) | 8 (1.1) | |||||
| Neck pain | 4 (0.4) | 8 (1.1) | |||||
| Osteoarthritis | 18 (1.8) | 5 (0.7) | |||||
| Pain in extremity | 23 (2.3) | 9 (1.2) |
|---|---|---|
| Shoulder pain | 7 (0.7) | 14 (1.9) |
| Nervous system disorders | ||
| Dizziness | 26 (2.7) | 14 (1.9) |
| Headache | 34 (3.5) | 31 (4.1) |
| Hypoaesthesia | 3 (0.3) | 11 (1.5) |
| Psychiatric disorders | ||
| Anxiety | 13 (1.3) | 7 (0.9) |
| Depression | 10 (1.0) | 7 (0.9) |
| Insomnia | 12 (1.2) | 11 (1.5) |
| Reproductive system and breast disorders | ||
| Erectile dysfunction | 6 (0.6) | 8 (1.1) |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 19 (1.9) | 23 (3.1) |
| Pharyngo laryngeal pain | 10 (1.0) | 9 (1.2) |
| Sinus congestion | 5 (0.5) | 8 (1.1) |
| Eczema | 4 (0.4) | 12 (1.6) |
| Vascular disorders | ||
| Hypertension | 33 (3.4) | 29 (3.9) |
Combination Therapy: Sitagliptin Add-on to Metformin and a Sulfonylurea
In a 24-week placebo-controlled study of sitagliptin 100 mg in combination with metformin and glimepiride (sitagliptin, N=116; placebo, N=113), the incidence of adverse events, reported regardless of causality assessment, in ≥1% of patients are shown in Table 4. The overall incidence of adverse events with sitagliptin was higher than with placebo, in part related to higher incidence of hypoglycemia (see Table 4).
Table 4 – Adverse Events ≥1% in Any Treatment Group (regardless of causality) Reported in Patients in a 24-Week Placebo-Controlled, Double-Blind Clinical Trial of Sitagliptin Add-on Combination Use with Metformin and a Sulfonylurea Agent (Glimepiride)
| Number of patients (%) | ||||||
|---|---|---|---|---|---|---|
| Body system/Organ class Adverse event | Sitagliptin 100 mg + Metformin + Glimepiride n=116 | Placebo + Metformin + Glimepiride n=113 | ||||
| Ear and Labyrinth Disorders | ||||||
| Vertigo | 2 (1.7) | 0 (0.0) | ||||
| Eye Disorders | ||||||
| Diabetic retinopathy | 0 (0.0) | 2 (1.8) | ||||
| Vision blurred | 0 (0.0) | 2 (1.8) | ||||
| Gastrointestinal disorders | ||||||
| Abdominal pain upper | 2 (1.7) | 2 (1.8) | ||||
| Constipation | 4 (3.4) | 0 (0.0) | ||||
| Diarrhea | 1 (0.9) | 4 (3.5) | ||||
| Dyspepsia | 3 (2.6) | 2 (1.8) | ||||
| Gastritis | 0 (0.0) | 4 (3.5) | ||||
| Toothache | 2 (1.7) | 2 (1.8) | ||||
| Vomiting | 2 (1.7) | 1 (0.9) |
|---|---|---|
| General disorders and administration site conditions | ||
| Fatigue | 0 (0.0) | 3 (2.7) |
| Non-Cardiac chest pain | 2 (1.7) | 1 (0.9) |
| Pyrexia | 0 (0.0) | 2 (1.8) |
| Hepatobiliary disorders | ||
| Cholelithiasis | 0 (0.0) | 2 (1.8) |
| Infections and infestations | ||
| Bronchitis | 2 (1.7) | 2 (1.8) |
| Gastroenteritis | 3 (2.6) | 0 (0.0) |
| Gastroenteritis viral | 2 (1.7) | 2 (1.8) |
| Influenza | 3 (2.6) | 2 (1.8) |
| Nasopharyngitis | 7 (6.0) | 9 (8.0) |
| Pharyngitis | 1 (0.9) | 3 (2.7) |
| Pneumonia | 3 (2.6) | 0 (0.0) |
| Rhinitis | 2 (1.7) | 0 (0.0) |
| Sinusitis | 1 (0.9) | 2 (1.8) |
| Tooth abscess | 2 (1.7) | 1 (0.9) |
| Upper respiratory tract infection | 8 (6.9) | 9 (8.0) |
| Urinary tract infection | 2 (1.7) | 1 (0.9) |
| Injury, poisoning and procedural complications | ||
| Fall | 0 (0.0) | 3 (2.7) |
| Poly traumatism | 1 (0.9) | 2 (1.8) |
| Investigations | ||
| Blood glucose decreased | 0 (0.0) | 2 (1.8) |
| Metabolism and nutrition disorders | ||
| Hypoglycemia | 19 (16.4) | 1 (0.9) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 5 (4.3) | 1 (0.9) |
| Back pain | 1 (0.9) | 2 (1.8) |
| Muscle spasms | 2 (1.7) | 1 (0.9) |
| Osteoarthritis | 2 (1.7) | 0 (0.0) |
| Pain in extremity | 4 (3.4) | 1 (0.9) |
| Shoulder pain | 0 (0.0) | 2 (1.8) |
| Nervous system disorders | ||
| Dizziness | 3 (2.6) | 1 (0.9) |
| Headache | 8 (6.9) | 3 (2.7) |
| Hypoaesthesia | 2 (1.7) | 0 (0.0) |
| Somnolence | 0 (0.0) | 2 (1.8) |
| Respiratory, thoracic and mediastinal disorders | ||
| Asthma | 2 (1.7) | 1 (0.9) |
| Skin and subcutaneous tissue disorders | ||
| Pruritus | 2 (1.7) | 1 (0.9) |
| Rash | 2 (1.7) | 1 (0.9) |
|---|---|---|
| Vascular disorders | ||
| Hypertension | 2 (1.7) | 0 (0.0) |
In a combination therapy study with metformin and a sulfonylurea, hypoglycemia (sitagliptin 13.8%; placebo 0.9%) and constipation (sitagliptin 1.7%; placebo 0.0%) were the only drug-related adverse reactions reported by the investigator that occurred with an incidence ≥1% in patients receiving sitagliptin and metformin and a sulfonylurea and greater than in patients receiving placebo and metformin and a sulfonylurea.
Combination Therapy: Add-on to Metformin and Insulin
In a 24-week placebo-controlled study of sitagliptin 100 mg once daily added to ongoing combination treatment with metformin and insulin (sitagliptin, N=229; placebo, N=233), the only adverse experience reported regardless of causality assessment in 5% of patients treated with sitagliptin and more commonly than in patients treated with placebo was hypoglycemia (sitagliptin 15.3%; placebo 8.2%).
Table 5 – Adverse Events ≥1% in Any Treatment Group (regardless of causality) Reported in Patients in a 24-Week Placebo-Controlled, Double-Blind Clinical Trial of Sitagliptin in Add-on Combination Use with Metformin and Insulin
| Number of patients (%) | ||||||
|---|---|---|---|---|---|---|
| Body system/Organ class Adverse event | Sitagliptin 100 mg + Metformin + Insulin n=229 | Placebo + Metformin + Insulin n=233 | ||||
| Gastrointestinal Disorders | ||||||
| Constipation | 4 (1.7) | 0 (0.0) | ||||
| Diarrhea | 4 (1.7) | 4 (1.7) | ||||
| Nausea | 2 (0.9) | 4 (1.7) | ||||
| Vomiting | 4 (1.7) | 2 (0.9) | ||||
General disorders and administration site conditions | ||||||
| Asthenia | 3 (1.3) | 1 (0.4) | ||||
| Fatigue | 0 (0.0) | 3 (1.3) | ||||
| Infections and infestations | ||||||
| Bronchitis | 5 (2.2) | 4 (1.7) | ||||
| Gastroenteritis | 1 (0.4) | 3 (1.3) | ||||
| Influenza | 9 (3.9) | 9 (3.9) | ||||
| Naso pharyngitis | 7 (3.1) | 7 (3.0) | ||||
| Respiratory tract infection | 3 (1.3) | 2 (0.9) | ||||
| Sinusitis | 2 (0.9) | 4 (1.7) | ||||
| Upper respiratory tract infection | 8 (3.5) | 10 (4.3) | ||||
| Urinary tract infection | 5 (2.2) | 5 (2.1) | ||||
| Viral infection | 0 (0.0) | 3 (1.3) | ||||
| Investigations | ||||||
| Creatinine renal clearance decreased | 3 (1.3) | 0 (0.0) | ||||
| Metabolism and nutrition disorders | ||
|---|---|---|
| Hypoglycemia | 35 (15.3) | 19 (8.2) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 1 (0.4) | 5 (2.1) |
| Muscle spasms | 0 (0.0) | 4 (1.7) |
| Musculoskeletal pain | 2 (0.9) | 3 (1.3) |
| Pain in extremity | 4 (1.7) | 2 (0.9) |
| Nervous system disorders | ||
| Dizziness | 2 (0.9) | 3 (1.3) |
| Headache | 3 (1.3) | 2 (0.9) |
Respiratory, thoracic and mediastinal disorders | ||
| Cough | 2 (0.9) | 3 (1.3) |
Combination Therapy: Sitagliptin Add-on to Metformin and Pioglitazone
In a 26-week placebo-controlled clinical study of patients receiving sitagliptin (100 mg daily) as add-on combination therapy with metformin and pioglitazone, the incidence of adverse events reported regardless of causality assessment, in ≥1% of patients are shown in Table 6.
Table 6 – Adverse Events ≥1% in Any Treatment Group (regardless of causality) Reported in Patients in a 26-Week Placebo-Controlled, Double-Blind Clinical Trial of Sitagliptin in Add-on Combination Use with Metformin and Pioglitazone
| Number of patients (%) | ||||||
|---|---|---|---|---|---|---|
| Body system/Organ class Adverse event | Sitagliptin 100 mg + Metformin + Pioglitazone n=157 | Placebo + Metformin + Pioglitazone n=156 | ||||
| Ear and Labyrinth Disorders | ||||||
| Cerumen impaction | 2 (1.3) | 1 (0.6) | ||||
| Eye Disorders | ||||||
| Conjunctivitis | 3 (1.9) | 1 (0.6) | ||||
| Ocularhyperaemia | 0 (0.0) | 2 (1.3) | ||||
| Gastrointestinal disorders | ||||||
| Abdominal pain upper | 1 (0.6) | 2 (1.3) | ||||
| Constipation | 2 (1.3) | 1 (0.6) | ||||
| Dental Caries | 2 (1.3) | 1 (0.6) | ||||
| Diarrhea | 3 (1.9) | 4 (2.6) | ||||
| Dyspepsia | 1 (0.6) | 2 (1.3) | ||||
| Gastritis | 0 (0.0) | 2 (1.3) | ||||
| Toothache | 2 (1.3) | 0 (0.0) | ||||
| Vomiting | 2 (1.3) | 0 (0.0) | ||||
General disorders and administration site conditions | ||||||
| Fatigue | 0 (0.0) | 2 (1.3) | ||||
| Oedema peripheral | 3 (1.9) | 7 (4.5) | ||||
| Infections and infestations | ||||||
| Bronchitis | 3 (1.9) | 1 (0.6) | ||||
| Cellulitis | 2 (1.3) | 0 (0.0) |
|---|---|---|
| Gastroenteritis | 2 (1.3) | 0 (0.0) |
| Gastroenteritis viral | 2 (1.3) | 0 (0.0) |
| Herpes zoster | 2 (1.3) | 0 (0.0) |
| Influenza | 2 (1.3) | 3 (1.9) |
| Nasopharyngitis | 5 (3.2) | 5 (3.2) |
| Tooth abscess | 0 (0.0) | 2 (1.3) |
| Upper respiratory tract infection | 13 (8.3) | 14 (9.0) |
| Urinary tract infection | 5 (3.2) | 6 (3.8) |
| Injury, poisoning and procedural complications | ||
| Muscle strain | 2 (1.3) | 0 (0.0) |
| Investigations | ||
| Blood creatine phosphokinase increased | 1 (0.6) | 3 (1.9) |
| Glomerular filtration rate decreased | 2 (1.3) | 0 (0.0) |
| Lymphocyte count increased | 2 (1.3) | 1 (0.6) |
| Neutrophil count decreased | 2 (1.3) | 1 (0.6) |
| Metabolism and nutrition disorders | ||
| Hyperglycemia | 2 (1.3) | 2 (1.3) |
| Hypoglycemia | 10 (6.4) | 7 (4.5) |
| Musculoskeletal and connective tissue disorders | ||
| Arthralgia | 2 (1.3) | 3 (1.9) |
| Back pain | 7 (4.5) | 4 (2.6) |
| Muscle spasms | 2 (1.3) | 0 (0.0) |
| Musculoskeletal pain | 3 (1.9) | 4 (2.6) |
| Pain in extremity | 5 (3.2) | 2 (1.3) |
| Nervous system disorders | ||
| Headache | 1 (0.6) | 2 (1.3) |
| Psychiatric disorders | ||
| Depression | 4 (2.5) | 1 (0.6) |
| Stress | 2 (1.3) | 0 (0.0) |
| Respiratory, thoracic and mediastinal disorders | ||
| Cough | 2 (1.3) | 2 (1.3) |
| Oropharyngeal pain | 2 (1.3) | 0 (0.0) |
| Rhinitis allergic | 2 (1.3) | 0 (0.0) |
In a combination therapy study with metformin and pioglitazone, hypoglycemia (sitagliptin 3.2%; placebo 1.9%), was the only drug-related adverse reaction reported by the investigator that occurred with an incidence ≥1% in patients receiving sitagliptin and greater than in patients receiving placebo.
8.2.1 Clinical Trial Adverse Reactions - Pediatrics
In clinical trials with sitagliptin and metformin hydrochloride in pediatric patients aged 10 to 17 years with type 2 diabetes mellitus, the profile of adverse reactions was generally comparable to that observed in adults. In pediatric patients, sitagliptin and metformin hydrochloride was associated with an increased risk of hypoglycaemia regardless of background insulin therapy.
8.3 Less Common Clinical Trial Adverse Reactions
Less Common Clinical Trial Adverse Drug Reactions ≥0. 1% and <1% (Drug-Related and Greater than Placebo)
Blood and Lymphatic System Disorders: anemia
Cardiac Disorders: bundle branch block, palpitations
Eye Disorders: vision blurred
Gastrointestinal Disorders: abdominal discomfort, abdominal pain upper, abdominal tenderness, constipation, diarrhea, dry mouth, dyspepsia, flatulence, irritable bowel syndrome, reflux esophagitis disease, frequent bowel movements, retching, salivary hypersecretion
General Disorders and Administration Site Conditions: asthenia, chest discomfort, face edema, hunger, irritability, malaise, peripheral edema, pain, pyrexia, thirst, xerosis
Hepatobiliary Disorders: hepatic steatosis
Infections and Infestations: gastric ulcer helicobacter, genital abscess, helicobacter gastritis, localized infection, oropharyngeal candidiasis, upper respiratory tract infection, urinary tract infection
Investigations: alanine aminotransferase increased, aspartate aminotransferase increased, blood glucose decreased, blood glucose increased, blood pressure decreased, blood pressure increased, creatinine renal clearance decreased, glomerular filtration rate decreased, white blood cell count increased
Metabolism and Nutrition Disorders: decreased appetite, hypoglycemia
Musculoskeletal and Connective Tissue Disorders: muscle tightness, muscle fatigue
Nervous System Disorders: coordination abnormal, dizziness, headache, migraine, neuropathy peripheral, parosmia, somnolence
Psychiatric Disorders: anxiety, depression, insomnia, libido decreased
Renal and Urinary Disorders: renal disorders
Reproductive System and Breast Disorders: balanoposthitis, dysmenorrhea, erectile dysfunction
Respiratory, Thoracic and Mediastinal Disorders: cough
Skin and Subcutaneous Tissue Disorders: angioneurotic oedema, dermatitis acneiform, dry skin, erythema, exanthem, hyperhidrosis, leukocytoclastic vasculitis, nail disorder, prurigo, pruritus generalized, rash, rash macular, rosacea, urticaria
Vascular Disorders: orthostatic hypotension
Atrial fibrillation/atrial flutter: In a pooled analysis of randomized clinical trials, the pooled termsatrial fibrillation/atrial flutter were observed at an incidence rate of 0.45 events per 100 patient-years in the sitagliptin-exposed group compared to 0.28 events per 100 patient-years in the non-exposed group.
TECOS Cardiovascular Safety Study:
For details pertaining to study design and patient population, see 14 CLINICAL TRIALS, TECOS Cardiovascular Safety Study.
The incidence of adjudication-confirmed pancreatitis events was higher in the sitagliptin group (0.3%) compared to the placebo group (0.2%). The sitagliptin group experienced a greater number of severe cases of pancreatitis including two confirmed deaths due to pancreatitis, compared to none in the placebo group.
Among patients who were using insulin and/or a sulfonylurea at baseline, the incidence of severe hypoglycemia was 2.7% in sitagliptin-treated patients and 2.5% in placebo-treated patients; among patients who were not using insulin and/or a sulfonylurea at baseline, the incidence of severe hypoglycemia was 1.0% in sitagliptin-treated patients and 0.7% in placebo-treated patients.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
Sitagliptin
The incidence of laboratory adverse experiences was similar in patients treated with sitagliptin 100 mg compared to patients treated with placebo. In most clinical studies, a slight decrease in alkaline phosphatase and small increases in uric acid and white blood cell (WBC) count (due to an increase in neutrophils) were observed. In active comparator studies versus a sulfonylurea agent (glipizide) similar changes were seen in alkaline phosphatase and uric acid.
| Mean Change from Baseline (Standard Error) | ||||
|---|---|---|---|---|
| Study | Treatment Group | Alkaline Phosphatase (IU/L) | Uric Acid (mg/dL) | WBC (cell/microl) |
| Placebo-controlled1 | Sitagliptin | -3.1 (0.4) | 0.17 (0.04) | 346.0 (64.3) |
| Placebo | -1.3 (0.7) | 0.05 (0.06) | 142.4 (98.8) | |
| Active-controlled2 | Sitagliptin | -5.7 (0.5) | 0.21 (0.05) | 207.8 (67.4) |
| Glipizide | -3.4 (0.5) | 0.20 (0.05) | 86.0 (62.5) | |
1 Sitagliptin in Combination with Metformin – Placebo-Controlled Study, see 14 CLI NICAL TRI ALS
2 Sitagliptin in Combination with Metformin – Active-Controlled (Sulfonylurea Agent) Study, see 14 CLINICAL
TRIALS
In a combination therapy study with insulin and metformin, a greater proportion of patients were observed to have a decrease in hemoglobin ≥1.5 g/dL in the sitagliptin group (6.8%) compared with the placebo group (2.3%).
Metformin hydrochloride
During controlled clinical trials of 29 weeks duration, approximately 9% of patients on metformin monotherapy developed asymptomatic subnormal serum vitamin B12 levels; serum folic acid levels did not decrease significantly. Five cases of megaloblastic anemia have been reported with metformin administration and no increased incidence of neuropathy has been observed. However, serious cases of peripheral neuropathy have been reported with metformin treatment in the post-marketing experience in patients with vitamin B12 deficiency (see 7 WARNINGS AND PRECAUTIONS and 8.5 ADVERSE REACTIONS, Post-Market Adverse Reactions).
8.5 Post-Market Adverse Reactions
Because these reactions are reported voluntarily from a population of uncertain size, it is generally not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Blood and lymphatic system disorders: hemolytic anemia, some with a fatal outcome (see 7 WARNINGS AND PRECAUTIONS)
Gastrointestinal disorders: abdominal discomfort, abdominal distension, abdominal pain, abdominal pain upper, acute pancreatitis, including fatal and non-fatal hemorrhagic and necrotizing pancreatitis (see 7 WARNINGS AND PRECAUTIONS), constipation, diarrhea, dry mouth, dyspepsia, flatulence, gastric disorder, gastric ulcer, gastrointestinal disorder, nausea, vomiting
Hepatobiliary disorders: liver function tests abnormalities or hepatitis resolving upon metformin discontinuation, autoimmune hepatitis, drug-induced liver injury, hepatitis (see 7 WARNINGS AND PRECAUTIONS)
Immune system disorders: hypersensitivity reactions including anaphylaxis, angioedema, rash, urticaria, cutaneous vasculitis and exfoliative skin conditions, including Stevens-Johnson syndrome (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS)
Investigations: blood lactic acid increased, reduction of thyrotropin level in patients with treated or untreated hypothyroidism (see 7 WARNINGS AND PRECAUTIONS)
Metabolism and nutrition disorders: lactic acidosis, decrease of vitamin B12 absorption with decrease of serum levels during long-term use of metformin, weight decreased, decreased appetite, peripheral neuropathy in patients with vitamin B12 deficiency, hypomagnesemia in the context of diarrhea (see 7 WARNINGS AND PRECAUTIONS)
Musculoskeletal and connective tissue disorders: arthralgia, myalgia, pain in extremity, back pain, rhabdomyolysis
Nervous system disorders: encephalopathy (see 7 WARNINGS AND PRECAUTIONS), headache
Renal and urinary disorders: worsening renal function, including acute renal failure (sometimes requiring dialysis) (see 7 WARNINGS AND PRECAUTIONS)
Skin and subcutaneous tissue disorder: photosensitivity, erythema, pruritus, rash, skin lesion, urticaria, bullous pemphigoid (see 7 WARNINGS AND PRECAUTIONS)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Pharmacokinetic drug interaction studies with sitagliptin and metformin hydrochloride have not been performed; however, such studies have been conducted with the individual sitagliptin and metformin components of sitagliptin and metformin hydrochloride.
The simultaneous administration of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride and a sulfonylurea could produce a hypoglycemic reaction, especially if they are given in patients already receiving other drugs which, themselves, can potentiate the effect of sulfonylureas. These drugs can be: long-acting sulfonamides, tubercolostatics, phenylbutazone, clofibrate, monoamine oxidase inhibitors, salicylates, probenecid and propanolol.
Sitagliptin
In Vitro Assessment of Drug Interactions: Sitagliptin is not an inhibitor of CYP isozymes CYP3A4, 2C8, 2C9, 2D6, 1A2, 2C19 or 2B6, and is not an inducer of CYP3A4. Sitagliptin is a p-glycoprotein substrate, but does not inhibit p-glyco protein mediated transport of digoxin. Based on these results, sitagliptin is considered unlikely to cause interactions with other drugs that utilize these pathways.
Sitagliptin is not extensively bound to plasma proteins. Therefore, the propensity of sitagliptin to be involved in clinically meaningful drug-drug interactions mediated by plasma protein binding displacement is very low.
Metformin hydrochloride
In Vivo Assessment of Drug Interactions: In healthy volunteers, the pharmacokinetics of propranolol and ibuprofen were not affected by metformin when co-administered in single-dose interaction studies. Metformin is negligibly bound to plasma proteins and is therefore, less likely to interact with highly protein-bound drugs such as salicylates, sulfonamides, chloramphenicol and probenecid, as compared to sulfonylureas, which are extensively bound to serum protein.
9.3 Drug-Behavioural Interactions
Effects of Smoking, Alcohol, and Diet: The effects of smoking, diet, and alcohol use on the pharmacokinetics of sitagliptin and metformin hydrochloride have not been specifically studied.
Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride, since alcohol intake potentiates the effect of metformin on lactate metabolism (see 2 CONTRAINDICATIONS). The risk of lactic acidosis is increased in acute alcohol intoxication, particularly in case of fasting or malnutrition or hepatic insufficiency. It is recommended that consumption of alcohol and alcohol-containing medicinal product be avoided.
9.4 Drug-Drug Interactions
Sitagliptin
In clinical studies, as described below, sitagliptin did not meaningfully alter the pharmacokinetics of metformin, glyburide, simvastatin, rosiglitazone, warfarin, or oral contraceptives, providing in vivo evidence of a low propensity for causing drug interactions with substrates of CYP3A4, CYP2C8, CYP2C9, and organic cationic transporter (OCT). Multiple doses of sitagliptin slightly increased digoxin concentrations; however, these increases are not considered likely to be clinically meaningful and are not attributed to a specific mechanism.
Effects of other drugs on the pharmacokinetics of sitagliptin
Metformin: Co-administration of multiple twice-daily doses of metformin with sitagliptin did not meaningfully alter the pharmacokinetics of sitagliptin in patients with type 2 diabetes.
Cyclosporine: A study was conducted to assess the effect of cyclosporine, a potent inhibitor of p- glycoprotein, on the pharmacokinetics of sitagliptin. Co-administration of a single 100 mg oral dose of sitagliptin and a single 600 mg oral dose of cyclosporine increased the area under the plasma concentration versus time curve (AUC) and Cmax of sitagliptin by approximately 29% and 68%, respectively. These modest changes in sitagliptin pharmacokinetics were not considered to be clinically meaningful. The renal clearance of sitagliptin was also not meaningfully altered. Therefore, meaningful interactions would not be expected with other p-glycoprotein inhibitors.
Effects of sitagliptin on the pharmacokinetics of other drugs
Metformin: Co-administration of multiple twice-daily doses of sitagliptin with metformin, an OCT substrate, did not meaningfully alter the pharmacokinetics of metformin or sitagliptin in patients with type 2 diabetes. Therefore, sitagliptin is not an inhibitor of OCT-mediated transport.
Sulfonylureas: Single-dose pharmacokinetics of glyburide, a CYP2C9 substrate, were not meaningfully altered in subjects receiving multiple doses of sitagliptin. Clinically meaningful interactions would not be expected with other sulfonylureas (e.g., glipizide, tolbutamide, and glimepiride) which, like glyburide, are primarily eliminated by CYP2C9.
Simvastatin: Single-dose pharmacokinetics of simvastatin, a CYP3A4 substrate, were not meaningfully altered in subjects receiving multiple daily doses of sitagliptin. Therefore, sitagliptin is not an inhibitor of CYP3A4-mediated metabolism.
Thiazolidinediones: Single-dose pharmacokinetics of rosiglitazone were not meaningfully altered in subjects receiving multiple daily doses of sitagliptin. Therefore, sitagliptin is not an inhibitor of CYP2C8-mediated metabolism. Clinically meaningful interactions with pioglitazone are not expected because pioglitazone predominantly undergoes CYP2C8- or CYP3A4-mediated metabolism.
Warfarin: Multiple daily doses of sitagliptin did not meaningfully alter the pharmacokinetics, as assessed by measurement of S(-) or R(+) warfarin enantiomers, or pharmacodynamics (as assessed by measurement of prothrombin International Normalized Ratio) of a single dose of warfarin. Since S(-) warfarin is primarily metabolized by CYP2C9, these data also support the conclusion that sitagliptin is not a CYP2C9 inhibitor.
Oral Contraceptives: Co-administration with sitagliptin did not meaningfully alter the steady state pharmacokinetics of norethindrone or ethinyl estradiol.
Digoxin: Sitagliptin had a minimal effect on the pharmacokinetics of digoxin. Following administration of 0.25 mg digoxin concomitantly with 100 mg of sitagliptin daily for 10 days, the plasma AUC of digoxin was increased by 11%, and the plasma Cmax by 18%. These increases are not considered likely to be clinically meaningful.
Metformin
Carbonic Anhydrase Inhibitors: Topiramate or other carbonic anhydrase inhibitors (e.g., zonisamide, acetazolamide or dichlorphenamide) frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Concomitant use of these drugs with Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride may increase the risk of lactic acidosis. Consider more frequent monitoring of these patients.
Glyburide: Ina single-dose interaction study in type 2 diabetes patients, co-administration of metformin and glyburide did not result in any changes in either metformin pharmacokinetics or pharmacodynamics. Decreases in glyburide AUC and Cmax were observed, but were highly variable. The single-dose nature of this study and the lack of correlation between glyburide blood levels and pharmacodynamic effects make the clinical significance of this interaction uncertain.
Furosemide: A single-dose, metformin-furosemide drug interaction study in healthy subjects demonstrated that pharmacokinetic parameters of both compounds were affected by co- administration. Furosemide increased the metformin plasma and blood Cmax by 22% and blood AUC by 15%, without any significant change in metformin renal clearance. When administered with metformin, the Cmax and AUC of furosemide were 31% and 12% smaller, respectively, than when administered alone, and the terminal half-life was decreased by 32%, without any significant change in furosemide renal clearance. No information is available about the interaction of metformin and furosemide when co-administered chronically.
Nifedipine: A single-dose, metformin-nifedipine drug interaction study in normal healthy volunteers demonstrated that co-administration of nifedipine increased plasma metformin Cmax and AUC by 20% and 9%, respectively, and increased the amount excreted in the urine. Tmax and half-life were unaffected. Nifedipine appears to enhance the absorption of metformin. Metformin had minimal effects on nifedipine.
Drugs that reduce metformin clearance: Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) could increase systemic exposure to metformin and may increase the risk for lactic acidosis (see 7 WARNINGS AND PRECAUTIONS). In both single- and multiple-dose metformin- cimetidine drug interaction studies, there was a 60% increase in peak metformin plasma and whole blood concentrations and a 40% increase in plasma and whole blood metformin AUC. There was no change in elimination half-life in the single-dose study. Metformin had no effect on cimetidine pharmacokinetics. Close monitoring of glycemic control, dose adjustment within the recommended posology and changes in diabetic treatment should be considered when such products are co-administered.
Levothyroxine: Levothyroxine can reduce the glucose-lowering effect of metformin. Monitoring of blood glucose levels is recommended, especially when thyroid hormone therapy is initiated, changed, or stopped (see 7 WARNINGS AND PRECAUTIONS), and Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride dosage adjusted as necessary.
Anticoagulant: Elimination rate of the anticoagulant phenprocoumon has been reported to be increased by 20% when used concurrently with metformin. Therefore, a close monitoring of the International Normalized Ratio (INR) is recommended in patients concurrently administering metformin and phenprocoumon or other antivitamin K anticoagulants (see 7 WARNINGS AND PRECAUTIONS). In such cases, an important increase of prothrombin time may occur upon cessation of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride therapy, with an increased risk of hemorrhage.
Other: Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, estrogen plus progestogen, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, isoniazid and beta-2-agonists.
ACE-inhibitors may decrease the blood glucose levels. When such drugs are administered to a patient receiving Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride the patient should be closely observed to maintain adequate glycemic control.
Diuretics, especially loop diuretics, may increase the risk of lactic acidosis due to their potential to decrease renal function.
9.5 Drug-Food Interactions
There are no known interactions with food.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Sitagliptin
Interactions with laboratory tests have not been established.
Metformin hydrochloride
Intravascular contrast studies with iodinated materials can lead to acute alteration of renal function and have been associated with lactic acidosis in patients receiving metformin (see
2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Sitagliptin and Metformin hydrochloride
Sitagliptin and metformin hydrochloride combine two antihyperglycemic agents with complementary mechanisms of action to improve glycemic control in patients with type 2 diabetes: sitagliptin, a dipeptidyl peptidase 4 (DPP-4) inhibitor, and metformin hydrochloride, a member of the biguanide class.
Sitagliptin and metformin hydrochloride targets three core defects of type 2 diabetes which are: decreased insulin synthesis and release, increased hepatic glucose production and decreased insulin sensitivity.
Sitagliptin
Sitagliptin is an orally-active, potent, and highly selective inhibitor of the dipeptidyl peptidase 4 (DPP-4) enzyme for the treatment of type 2 diabetes. The DPP-4 inhibitors are a class of agents that act as incretin enhancer.
Incretin hormones, including glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), are released by the intestine throughout the day, and levels are increased in response to a meal. The incretins are part of an endogenous system involved in the physiologic regulation of glucose homeostasis. When blood glucose concentrations are normal or elevated, GLP-1 and GIP increase insulin synthesis and release from pancreatic beta cells by intracellular signaling pathways involving cyclic AMP. Progressive beta-cell failure is a feature characterizing the pathogenesis of type 2 diabetes. Treatment with GLP-1 or with DPP-4 inhibitors in animal models of type 2 diabetes has been demonstrated to improve beta cell responsiveness to glucose and stimulate insulin biosynthesis and release. With higher insulin levels, tissue glucose uptake is enhanced.
In addition, GLP-1 lowers glucagon secretion from pancreatic alpha cells. Decreased glucagon concentrations, along with higher insulin levels, lead to reduced hepatic glucose production, resulting in a decrease in blood glucose levels. When blood glucose concentrations are low, stimulation of insulin release and suppression of glucagon secretion by GLP-1 are not observed. GLP-1 does not impair the normal glucagon response to hypoglycemia.
The activity of GLP-1 and GIP is limited by the DPP-4 enzyme, which rapidly hydrolyzes the incretin hormones to produce inactive products. Sitagliptin prevents the hydrolysis of incretin hormones by DPP- 4, thereby increasing plasma concentrations of the active forms of GLP-1 and GIP. By enhancing active incretin levels, sitagliptin increases insulin release and decreases glucagon levels in a glucose-dependent manner.
In patients with type 2 diabetes with hyperglycemia, these changes in insulin and glucagon levels lead to lower hemoglobin A1c (HbA1c) and lower fasting and postprandial glucose concentrations. Sitagliptin demonstrates selectivity for DPP-4, and does not inhibit the DPP-8 or DPP-9 activity in vitro at concentrations approximating those from therapeutic doses. Inhibition of DPP-8 or DPP-9, but not DPP- 4, is associated with toxicity in preclinical animal models and alteration of immune function in vitro.
Sitagliptin was assessed for its ability to improve glucose tolerance in lean and diet-induced obese (DIO) mice following dextrose challenge and in diabetic (db/db) mice. In lean and DIO mice, single oral doses of sitagliptin reduced blood glucose levels in a dosage-dependent manner. Acute lowering of blood glucose was also demonstrated in diabetic db/db mice. A 2- to 3-fold increase in active GLP-1 was seen at the maximally effective dose of 1 mg/kg sitagliptin in lean mice. These results are consistent with the action of sitagliptin as an anti-hyperglycemic agent.
Treatment with GLP-1 or with DPP-4 inhibitors in animal models of type 2 diabetes has been demonstrated to improve beta cell responsiveness to glucose, stimulate insulin biosynthesis and release, increase beta cell neogenesis, and decrease beta cell death. The effects on beta cell neogenesis and beta cell death have not been studied in humans.
Metformin hydrochloride
Metformin is a biguanide derivative producing an antihyperglycemic effect which can only be observed in man or in the diabetic animal and only when there is insulin secretion. Metformin, at therapeutic doses, does not cause hypoglycemia when used alone in man or in the non-diabetic animal, except when using a near lethal dose. Metformin has no effects on the pancreatic beta cells. The mode of action of metformin is not fully understood. It has been postulated that metformin might potentiate the effect of insulin or that it might enhance the effect of insulin on the peripheral receptor site. This increased sensitivity seems to follow an increase in the number of insulin receptors on cell surface membranes.
Metformin absorption is relatively slow and may extend over about 6 hours. Animal studies with metformin, labelled with 14C have shown that the drug is neither concentrated by liver cells nor is it excreted in the bile; it is concentrated in the intestinal mucosa and salivary glands.
It has been shown that, following a 2 g dose of metformin, the blood level remains under 10 mcg/mL even at the peak, occurring 2 hours after absorption. During the experiments, metformin was shown to be devoid of any notable action in the body, apart from its specific metabolic activity.
In the healthy animal, metformin lowers blood sugar only at a nearly lethal dose. Different animal species are of unequal sensitivity. On the other hand, the animal with experimental diabetes, is sensitive to a much lower dosage, providing some insulin is still secreted.
The antihyperglycemic action of metformin is probably mediated through insulin:
Metformin improves the K co-efficient of glucose as simulation.
Metformin improves the co-efficient of insulin efficiency.
In the obese diabetic with hyperinsulinemia, metformin is reported to normalize insulin output. This normalizing effect is concurrent to that of glycemia.
Metformin has little effect on liver glycogen of the healthy animal. In low and average doses, no change occurs. In high doses nearing lethal levels, liver glycogen decreases. This lowering precedes the fall in blood sugar. This reaction represents a defense mechanism tending to mobilize body reserves in order to combat hypoglycemia.
In the diabetic animal with a low liver glycogen reserve, the opposite occurs and metformin builds up glycogen stores of the liver. In vitro, on muscular tissue isolated in Warburg’s apparatus, metformin increases glucose uptake by the muscle. This action follows an aerobic pathway. Even in high concentration, contrary to phenethyl-biguanide, metformin apparently does not block respiration or change carbohydrate metabolism via the anaerobic pathway.
Metformin is eliminated in faeces and urine. It is rapidly excreted by the kidneys in an unchanged form. Renal clearance is 450 mL/minute; this appears to explain the absence of accumulation.
Metabolites of metformin have not been identified, neither by radio-active nor by chemical methods.
A single Rf spot is always present following radiochromatographic study of urine and always corresponds to that of pure metformin. Administration during 10 consecutive days has not shown any sign of accumulation.
Inhibition of glyconeogenesis has been observed in animals following its stimulation by fasting, cortisol, alcohol or other substrates such as alanine lactate or pyruvate. However, such an effect varies according to the type and dosage of the biguanide used, nutritional state of the animal species and design of experimental model.
This inhibition of glyconeogenesis is observed only in the presence of insulin and it does not appear to play an important role in man.
Inhibition of intestinal absorption of sugars, which is not related to a malabsorption phenomenon has been observed with biguanides under certain experimental conditions in animal and in man. In one study, a 20% retardation of galactose absorption was observed in man receiving metformin. However, such an effect of metformin could not be confirmed in another study in man.
Recent findings appear to indicate that most of the metabolic effects of the biguanides are exerted through a single mechanism, namely inhibition of fatty acid oxidation and of acetyl-CoA generation.
However, inhibition of insulin-stimulated lipogenesis which has also been observed appears to be due to the inhibition of acetyl-CoA carboxylase by the biguanides. Such an effect may explain, at least partly, the weight-reducing effect exerted by these drugs in obese diabetic patients.
10.2 Pharmacodynamics
Sitagliptin
In patients with type 2 diabetes, administration of single oral doses of sitagliptin leads to inhibition of DPP-4 enzyme activity for a 24-hour period, resulting in a 2- to 3-fold increase in circulating levels of active GLP-1 and GIP, increased plasma levels of insulin and C-peptide, decreased glucagon concentrations, reduced fasting glucose, and reduced glucose excursion following an oral glucose load or a meal.
In a study of patients with type 2 diabetes inadequately controlled on metformin monotherapy, glucose levels monitored throughout the day were significantly lower (p<0.001) in patients who received sitagliptin 100 mg per day (50 mg twice daily) in combination with metformin compared with patients who received placebo with metformin (see Figure 1).
Figure 1 – 24-Hour Plasma Glucose Profile after 4-Week Treatment with Sitagliptin 50 mg BID with Metformin or Placebo with Metformin
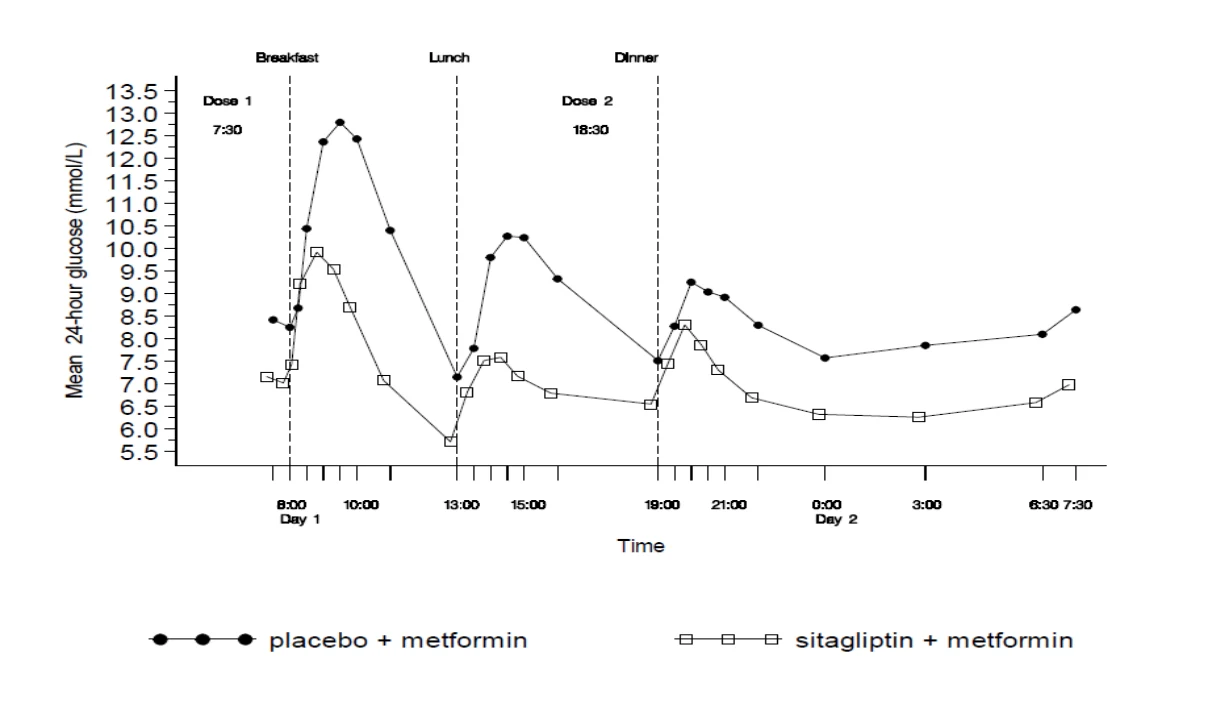
In studies with healthy subjects, sitagliptin did not lower blood glucose or cause hypoglycemia, suggesting that the insulinotropic and glucagon suppressive actions of the drug are glucose dependent.
Cardiac Electrophysiology: Ina randomized, placebo-controlled crossover study, 79 healthy subjects were administered a single oral dose of sitagliptin 100 mg, sitagliptin 800 mg (8 times the recommended dose), and placebo. At the recommended dose of 100 mg, there was no effect on the QTc interval obtained at the peak plasma concentration, or at any other time during the study. Following the 800 mg dose, the maximum increase in the placebo-corrected mean change in QTc from baseline at 3 hours post-dose was 8.0 msec (90% CI; 5.5, 10.6). At the 800 mg dose, peak sitagliptin plasma concentrations were approximately 11times higher than the peak concentrations following a 100 mg dose.
In patients with type 2 diabetes administered sitagliptin 100 mg (N=81) or sitagliptin 200 mg (N=63) daily, there were no meaningful changes in QTc interval based on ECG data obtained at the time of expected peak plasma concentration.
Metformin hydrochloride
Few data are available on the relationship between pharmacodynamics and pharmacokinetics, and therefore the effect of metformin on glucose control cannot be predicted from pharmacokinetic data alone. Tissue concentrations of metformin in the dual target sites of the liver and muscle appear to be more informative, and the deep metformin compartment supplying these tissues is critical and related to plasma concentrations. This view substantiates the clinical observation that the glucose-lowering action of metformin takes time to be fully expressed and also that activity is not lost immediately on drug withdrawal.
Sitagliptin and Metformin Co-Administration
In a two-day study in healthy subjects, sitagliptin alone increased active GLP-1 concentrations, whereas metformin alone increased active and total GLP-1 concentrations to similar extents. Co-administration of sitagliptin and metformin has an additive effect on active GLP-1 concentrations. Sitagliptin, but not metformin, increased active GIP concentrations. It is unclear what these findings mean for changes in glycemic control in patient with type 2 diabetes.
10.3 Pharmacokinetics
Sitagliptin and Metformin Hydrochloride
In a bioequivalence study of sitagliptin and metformin hydrochloride 50/500 and 50/1000 (mg/mg sitagliptin/metformin hydrochloride), both the sitagliptin component and the metformin component were bioequivalent to co-administered 50 mg sitagliptin tablet and metformin hydrochloride tablets 500 and 1000 mg, respectively under fasted conditions in healthy subjects.
Because bioequivalence is demonstrated at the lowest and highest combination tablet dose strengths available, bioequivalence is conferred to the (sitagliptin/metformin) 50 mg/850 mg fixed dose combination (FDC) tablet.
Table 7 – Geometric Mean Pharmacokinetic Parameters for Sitagliptin and Metformin Following Single Dose of sitagliptin and metformin hydrochloride or Co-administration of Corresponding Doses of Sitagliptin and Metformin as Individual Tablets to Healthy Subjects Under Fasted Conditions
| Sitagliptin | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Treatment | Subject Number | AUC0-∞ (mcM·hr) | Cmax (nM) | Tmax † (hr) | t1/2‡ (hr) | ||||||||||
| A | 24 | 4.09 | 415 | 2.50 | 12.3 | ||||||||||
| B | 24 | 4.01 | 414 | 2.75 | 12.6 | ||||||||||
| C | 24 | 4.05 | 423 | 2.50 | 13.1 | ||||||||||
| D | 24 | 3.94 | 397 | 2.50 | 13.7 | ||||||||||
| Metformin | |||||||||||||||
| Treatment | Subject Number | AUC0-∞ (mcg/mL·hr) | Cmax (ng/mL) | Tmax † (hr) | t1/2‡ (hr) | ||||||||||
| A | 24 | 7.26 | 1180 | 2.50 | 9.79 | ||||||||||
| B | 24 | 7.25 | 1180 | 2.75 | 11.6 | ||||||||||
| C | 24 | 11.9 | 1850 | 2.50 | 13.6 | ||||||||||
| D | 24 | 11.9 | 1870 | 2.00 | 13.9 | ||||||||||
† Median ‡ Harmonic Mean Treatment A = sitagliptin 50 mg + metformin hydrochloride 500 mg Treatment B = sitagliptin and metformin hydrochloride sitagliptin (50 mg)/metformin hydrochloride (500 mg) Treatment C = sitagliptin 50 mg + metformin hydrochloride 1000 mg Treatment D = sitagliptin and metformin hydrochloride sitagliptin (50 mg)/metformin hydrochloride (1000 mg) | |||||||||||||||
When administered in the fed state (following a standard high-fat breakfast), the metformin component of sitagliptin and metformin hydrochloride was bioequivalent to metformin taken together with sitagliptin as individual tablets.
Absorption:
Sitagliptin
The absolute bioavailability of sitagliptin is approximately 87%. Co-administration of a high-fat meal with sitagliptin had no effect on the pharmacokinetics of sitagliptin.
Metformin hydrochloride
Metformin absorption is relatively slow and may extend over about 6 hours.
Distribution:
Sitagliptin
The mean volume of distribution at steady state following a single 100 mg intravenous dose of sitagliptin to healthy subjects is approximately 198 liters. The fraction of sitagliptin reversibly bound to plasma proteins is low (38%).
Metformin hydrochloride
Plasma protein binding is negligible. Metformin partitions into erythrocytes. The blood peak is lower than the plasma peak and appears at approximately the same time. The red blood cells most likely represent a secondary compartment of distribution. The mean volume of distribution (Vd) ranged between 63-276 l.
Metabolism:
Sitagliptin
Sitagliptin is primarily eliminated unchanged in urine, and metabolism is a minor pathway. Approximately 79% of sitagliptin is excreted unchanged in the urine.
Following a [14C] sitagliptin oral dose, approximately 16% of the radioactivity was excreted as metabolites of sitagliptin. Six metabolites were detected at trace levels and are not expected to contribute to the plasma DPP-4 inhibitory activity of sitagliptin. In vitro studies indicated that the primary enzyme responsible for the limited metabolism of sitagliptin was CYP3A4, with contribution from CYP2C8.
Metformin hydrochloride
Metformin is not metabolized. Its main sites of concentration are the intestinal mucosa and the salivary glands. The plasma concentration at steady-state ranges about 1 to 2 mcg/mL. Certain drugs may potentiate the effects of metformin (see 7 WARNINGS AND PRECAUTIONS and 9 DRUG INTERACTIONS).
Elimination:
Sitagliptin
Following administration of an oral [14C] sitagliptin dose to healthy subjects, approximately
100% of the administered radioactivity was eliminated in feces (13%) or urine (87%) within one week of dosing. The apparent terminal t1/2 following a 100-mg oral dose of sitagliptin was approximately 12.4 hours and renal clearance was approximately 350 mL/min.
Elimination of sitagliptin occurs primarily via renal excretion and involves active tubular secretion. Sitagliptin is a substrate for human organic anion transporter-3 (hOAT-3), which may be involved in the renal elimination of sitagliptin. The clinical relevance of hOAT-3 in sitagliptin transport has not been established. Sitagliptin is also a substrate of p-glycoprotein, which may also be involved in mediating the renal elimination of sitagliptin. However, cyclosporine, a p-glycoprotein inhibitor, did not reduce the renal clearance of sitagliptin.
Metformin hydrochloride
The drug is excreted in urine at high renal clearance rate of about 450 mL/min. The initial elimination of metformin is rapid with a half-life varying between 1.7 and 3 hours. The terminal elimination phase accounting for about 4 to 5 % of the absorbed dose is slow with a half-life between 9 and 17 hours.
Special Populations and Conditions
- Pediatrics:
The pharmacokinetics of sitagliptin (single dose of 50 mg, 100 mg or 200 mg) were investigated in pediatric patients (10 to 17 years of age) with type 2 diabetes. In this population, the dose- adjusted AUC of sitagliptin in plasma was approximately 18% lower compared to adult patients with type 2 diabetes for a 100 mg dose.
No studies with sitagliptin have been performed in pediatric patients < 10 years of age. Health Canada has not authorized an indication for pediatric use.
- Geriatrics:
Sitagliptin
Age did not have a clinically meaningful impact on the pharmacokinetics of sitagliptin based on a population pharmacokinetic analysis of Phase I and Phase II data. Elderly subjects (65 to
80 years) had approximately 19% higher plasma concentrations of sitagliptin compared to younger subjects.
Metformin hydrochloride
Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients.
Limited data from controlled pharmacokinetic studies of metformin hydrochloride in healthy elderly subjects suggest that total plasma clearance of metformin is decreased, the half-life is prolonged and Cmax is increased, compared to healthy young subjects. From these data, it appears that the change in metformin pharmacokinetics with aging is primarily accounted for by a change in renal function (see Warnings and Precautions, Special Populations).
- Sex:
Sitagliptin
Gender had no clinically meaningful effect on the pharmacokinetics of sitagliptin based on a composite analysis of Phase I pharmacokinetic data and on a population pharmacokinetic analysis of Phase I and Phase II data.
Metformin hydrochloride
In the pharmacokinetic studies in healthy volunteers, there were no important differences between male and female subjects with respect to metformin AUC (males = 268, females = 293) and t½ (males = 229, females = 260). However, Cmax for metformin were somewhat higher in female subjects (Female/Male Cmax Ratio= 1.4). The gender differences for Cmax are unlikely to be clinically important.
Ethnic Origin:
Sitagliptin
Race had no clinically meaningful effect on the pharmacokinetics of sitagliptin based on a composite analysis of Phase I pharmacokinetic data and on a population pharmacokinetic analysis of Phase I and Phase II data, including subjects of White, Hispanic, Black and Asian racial groups.
- Hepatic Insufficiency:
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe hepatic impairment and should not be used in patients with clinical or laboratory evidence of hepatic disease (see 2 CONTRAINDICATIONS).
Sitagliptin
In patients with moderate hepatic impairment (Child-Pugh score 7 to 9), mean AUC and Cmax of sitagliptin increased approximately 21% (90% CI: 1%, 46%) and 13% (90% CI: -9%, 42%), respectively, compared to healthy matched controls following administration of a single 100 mg dose of sitagliptin.
Metformin hydrochloride
No pharmacokinetic studies of metformin have been conducted in patients with hepatic impairment.
Renal Insufficiency:
Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride is contraindicated in patients with severe renal impairment (eGFR <30 mL/min/1.73 m2) (see 2 CONTRAINDICATIONS).
Sitagliptin
A single-dose, open-label study was conducted to evaluate the pharmacokinetics of a reduced dose of sitagliptin (50 mg) in patients with varying degrees of chronic renal insufficiency compared to normal healthy control subjects. The study included patients with mild, moderate, and severe renal impairment, as well as patients with ESRD on hemodialysis. In addition, the effects of renal impairment on sitagliptin pharmacokinetics in patients with type 2 diabetes and mild, moderate or severe renal impairment (including ESRD) were assessed using population pharmacokinetic analyses.
Compared to normal healthy control subjects, an approximate 1.2 to 1.6-fold increase in plasma AUC of sitagliptin was observed in patients with mild renal impairment (eGFR ≥60 mL/min/1.73 m2 to <90 mL/min/1.73 m2) and patients with moderate renal impairment (eGFR ≥45 mL/min/1.73 m2 to <60 mL/min/1.73 m2), respectively, which is not a clinically meaningful increase to require dosage adjustment.
An approximately 2-fold increase in the plasma AUC of sitagliptin was observed in patients with moderate renal impairment (eGFR ≥30 mL/min/1.73 m2 to <45 mL/min/1.73 m2) and an approximately 4-fold increase was observed in patients with severe renal impairment (eGFR
<30 mL/min/1.73 m2) including patients with ESRD on hemodialysis, as compared to normal healthy control subjects.
To achieve plasma concentrations of sitagliptin similar to those in patients with normal renal function, lower dosages are recommended in patients with eGFR <45 mL/min/1.73 m2 (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
Metformin hydrochloride
In patients with decreased renal function, the plasma and blood half-life of metformin is prolonged and the renal clearance is decreased (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS).
11 STORAGE, STABILITY AND DISPOSAL
Stored at 15oC to 30oC.
PART II: SCIENTIFICINFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Sitagliptin Hydrochloride Monohydrate
Chemical Name: (3R)-3-amino-1-[5,6-dihydro-3-(trifluoromethyl)-1,2,4-triazolo[4,3-a]pyrazin-7-(8H)-yl]-4-(2,4,5-trifluorophenyl)-1-butanone, monohydrochloride Monohydrate.
Molecular Formula: C16H15F6N5O.HCl.H2O
Molecular Weight: 461.80 g/mol
Structural Formula:
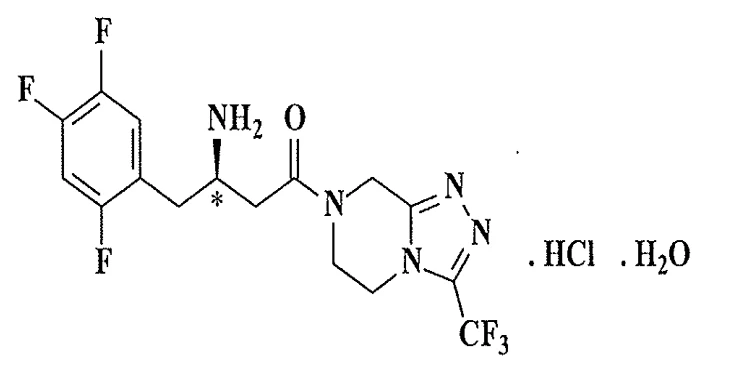
Physicochemical properties:
Description: A white (or) almost white powder.
Solubility: Freely Soluble in water and in methanol and practically insoluble in methylene chloride.
Proper name: Metformin hydrochloride
Chemical Name: 1,1-Dimethylbiguanide hydrochloride
Molecular Formula: C4H11N5 · HCl
Molecular Weight: 165.6 g/mol
Structural Formula:
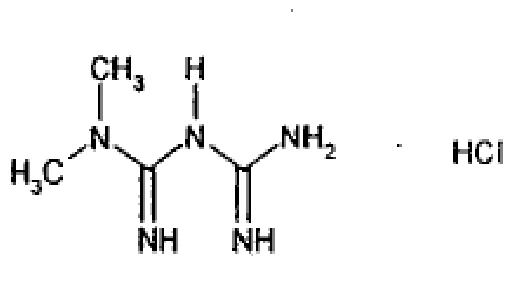
Physicochemical properties:
Description: White or almost White crystals.
Solubility: Freely soluble in water, slightly soluble in Alcohol, practically insoluble inn Acetone and in Methylene Chloride.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Clinical studies of the co-administration of sitagliptin and metformin demonstrated significant improvements in glycemic control in adult patients with type 2 diabetes. None of the clinical efficacy studies in adults described below were conducted with sitagliptin and metformin hydrochloride tablets; however, bioequivalence of sitagliptin and metformin hydrochloride tablets with co-administered sitagliptin and immediate-release metformin hydrochloride tablets has been demonstrated (see 10 CLINICAL PHARMACOLOGY).
The combination of sitagliptin and metformin has been evaluated for safety and efficacy in four double- blind, placebo-controlled studies and in one double-blind, active controlled clinical study in patients with type 2 diabetes mellitus. In all studies, patients with inadequate glycemic control on stable doses of metformin ≥1500 mg were randomized to receive either sitagliptin 100 mg per day, or placebo or an active comparator, in addition to ongoing background therapy.
Sitagliptin in Combination with Metformin
Placebo-Controlled Study
Table 8 – Summary of Study Design and Patient Demographic
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| P020 | Multicentre, randomized, double- blind, placebo- controlled | Sitagliptin 100 mg once daily+ ≥1500 mg/day Metformin or Placebo + ≥1500 mg/day Metformin Oral 24-week | 701 | 54.5 years (19–78) | Male: 400 Female: 301 |
A total of 701 patients with type 2 diabetes participated in a 24-week, randomized, double-blind, placebo-controlled study designed to assess the efficacy of sitagliptin in combination with metformin. All patients were started on metformin monotherapy and the dose increased to at least 1500 mg per day.
Patients were randomized to the addition of either 100 mg of sitagliptin or placebo, administered once daily. Patients with congestive heart failure requiring pharmacological treatment were excluded from this study.
In combination with metformin, sitagliptin provided significant improvements in HbA1c, FPG, and 2-hour PPG compared to placebo with metformin (Table 9). The improvement in HbA1c was not affected by baseline HbA1c, prior anti-hyperglycemic therapy, gender, age, baseline BMI, length of time since diagnosis of diabetes, presence of metabolic syndrome (according to NCEP criteria), or standard indices of insulin resistance (HOMA-IR) or insulin secretion (HOMA-β). Body weight decreased from baseline in both treatment groups.
| Table 9 – Glycemic Parameters and Body Weight at Final Visit (24 Week Study) for Sitagliptin in Combination with Metformin† | |||||||||
|---|---|---|---|---|---|---|---|---|---|
| Sitagliptin 100 mg + Metformin | Placebo + Metformin | ||||||||
| HbA1c (%) | N=453 | N=224 | |||||||
| Baseline(mean) | 8.0 | 8.0 | |||||||
| Change from baseline(adjusted mean‡) | -0.7 | -0.0 | |||||||
| Difference from placebo + metformin (adjusted mean‡) | -0.7§ | ||||||||
| Patients (%) achieving HbA1c <7% | 213 (47.0%) | 41 (18.3%) | |||||||
| FPG (mmol/L) | N=454 | N=226 | |||||||
| Baseline(mean) | 9.4 | 9.6 | |||||||
| Change from baseline(adjusted mean‡) | -0.9 | 0.5 | |||||||
| Difference from placebo + metformin (adjusted mean‡) | -1.4§ | ||||||||
| 2-hour PPG (mmol/L) | N=387 | N=182 | |||||||
| Baseline(mean) | 15.3 | 15.1 | |||||||
| Change from baseline(adjusted mean‡) | -3.4 | -0.6 | |||||||
| Difference from placebo + metformin (adjusted mean‡) | -2.8§ | ||||||||
| Body Weight (kg)* | N=399 | N=169 | |||||||
| Baseline(mean) | 86.9 | 87.6 | |||||||
| Change from baseline(adjusted mean‡) | -0.7 | -0.6 | |||||||
| Difference from placebo + metformin (adjusted mean‡) | -0.1¶ | ||||||||
† All Patients Treated Population (an intention-to-treat analysis).
‡ Least squares means adjusted for prior antihyperglycemic therapy and baseline value.
§ p<0.001 compared to placebo + metformin.
*All Patients as Treated (APaT) population, excluding patients given glycemic rescue therapy.
¶ Not statistically significant (p≥0.05) compared to placebo + metformin.
Active-Controlled (Sulfonylurea Agent) Study
Table 10 – Summary of Study Design and Patient Demographic
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| P024 | Multicentre, randomized, double- blind, with an active comparator | Sitagliptin 100 mg/day + ≥1500 mg/day Metformin or Glipizide 5–20 mg/ day + ≥1500 mg/day Metformin Oral 52-week | 1172 | Male 23–79 Female 22–78 | Male: 694 Female: 478 |
Long-term maintenance of effect was evaluated in a 52-week, double-blind, glipizide-controlled trial in patients with type 2 diabetes and inadequate glycemic control on metformin monotherapy at ≥1500 mg/day. In this study, patients were randomized to the addition of either sitagliptin 100 mg daily (N=588) or glipizide (N=584) for 52 weeks. Patients receiving glipizide were given an initial dosage of 5 mg/day and then electively titrated by the investigator to a target FPG of 6.1 mmol/L, without significant hypoglycemia, over the next 18 weeks. A maximum dosage of 20 mg/day was allowed to optimize glycemic control. Thereafter, the glipizide dose was to have been kept constant. The mean daily dose of glipizide after the titration period was 10.3 mg.
Both treatments resulted in a statistically significant improvement in glycemic control from baseline. After 52 weeks, the reduction from baseline in HbA1c was 0.67% for sitagliptin 100 mg daily and 0.67% for glipizide, confirming the non-inferiority of sitagliptin compared to glipizide. The reduction in FPG was 0.6 mmol/L for sitagliptin and 0.4 mmol/L for glipizide. In this study, the proinsulin to insulin ratio, a marker of efficiency of insulin synthesis and release, improved with sitagliptin relative to glipizide. The incidence of hypoglycemia in the sitagliptin group (4.9%) was significantly lower than that in the glipizide group (32.0%). Patients treated with sitagliptin exhibited a significant mean decrease from baseline in body weight compared to a significant weight gain in patients administered glipizide (-1.5 kg vs. +1.1 kg).
Sitagliptin Add-on Combination Therapy
Add-on Combination Therapy with Metformin plus Glimepiride
Table 11 – Summary of Study Design and Patient Demographic
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| P035 | Multicentre, randomized, double- blind, placebo-controlled | Sitagliptin 100 mg/day + Glimepiride ≥4 mg/day in combination with Metformin ≥1500 mg/day or Placebo + Glimepiride ≥4 mg/day in combination with Metformin ≥1500 mg/day Oral 24-week | 229 | 58.0 years (33–75) | Male: 120 Female: 109 |
In a 24-week, randomized, double-blind, placebo-controlled study designed to assess the efficacy of sitagliptin 100 mg once daily (N=116) compared to placebo (N=113), 229 patients were on the combination of glimepiride (≥4 mg per day) and metformin (≥1500 mg per day); the results of the glycemic endpoints, including HbA1c and FPG, are described below.
The combination of sitagliptin, glimepiride, and metformin provided significant reduction from baseline in HbA1c and FPG compared to placebo (see Table 12). Mean reductions from baseline in HbA1c compared with placebo were generally greater for patients with higher baseline HbA1c values. Patients treated with sitagliptin, had a modest increase in body weight (0.4 kg) compared to those given placebo who had a significant decrease in body weight (-0.7 kg).
Table 12 – Glycemic Parameters and Body Weight at Final Visit (24-Week Study) for Sitagliptin in Add-on Combination Therapy with Metformin plus Glimepiride†
Sitagliptin 100 mg + Metformin + Glimepiride | Placebo + Metformin + Glimepiride | |
|---|---|---|
| HbA1c (%) | N=115 | N=105 |
| Baseline(mean) | 8.27 | 8.28 |
| Change from baseline(adjusted mean‡) | -0.59 | 0.30 |
| Difference from placebo (adjusted mean‡) | -0.89§ | |
| Patients (%) achieving HbA1c <7% | 26 (22.6) | 1 (1.0) |
| PG (mmol/L) | N=115 | N=109 |
| Baseline(mean) | 9.95 | 9.93 |
| Change from baseline(adjusted mean‡) | -0.43 | 0.72 |
| Difference from placebo (adjusted mean‡) | -1.15§ | |
| Body Weight (kg)* | N=102 | N=74 |
| Baseline(mean) | 86.5 | 84.6 |
| Change from baseline(adjusted mean‡) | 0.4 | -0.7 |
| Difference from placebo (adjusted mean‡) | 1.1†† |
† All Patients Treated Population (an intention-to-treat analysis).
‡ Least squares means adjusted for prior antihyperglycemic therapy status and baseline value.
§ p<0.001 compared to placebo.
* All Patients as Treated (APaT) population, excluding patients given glycemic rescue therapy.
†† p=0.007 compared to placebo.
Add-on Combination Therapy with Metformin and Insulin
Table 13 – Summary of Study Design and Patient Demographic
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| P051 | Multicentre, randomized, double- blind placebo- controlled | Sitagliptin 100 mg/day + Stable dose insulin (alone or in combination with metformin ≥1500 mg/day) or Placebo + stable dose insulin(alone or in combination with metformin ≥1500 mg/day) 24-week | 641 | 57.8 years (25–82) | Male: 326 Female: 315 |
A total of 641 patients with type 2 diabetes participated in a 24-week, randomized, double-blind, placebo-controlled study designed to assess the efficacy of sitagliptin 100 mg once daily in combination with insulin. Approximately 75% (n=462) of patients were also taking metformin. Patients with an HbA1c of 7.5% to 11.0% while on a stable regimen of pre-mixed, long-acting or intermediate acting insulin, and metformin (≥1500 mg per day) were randomized to the addition of either 100 mg of sitagliptin or placebo. Patients using pre-meal short-acting or rapid-acting insulins that were not components of a pre-mixed insulin formulation, or that were administered via insulin pumps, were not included in this study. Glycemic endpoints measured included HbA1c, FPG and 2-hour PPG.
The combination of sitagliptin, metformin and insulin provided significant improvements in HbA1c, FPG and 2-hour PPG compared to placebo, metformin and insulin (Table 14). There was no meaningful change from baseline in body weight in either group.
Table 14 – Glycemic Parameters and Body Weight at Final Visit (24-Week Study) for Sitagliptin as Add- on Combination Therapy with Metformin and Insulin†
Sitagliptin 100 mg + Insulin + Metformin | Placebo + Insulin + Metformin | |
|---|---|---|
| HbA1c (%) | N=223 | N=229 |
| Baseline(mean) | 8.7 | 8.6 |
| Change from baseline(adjusted mean‡) | -0.7 | -0.1 |
| Difference from placebo (adjusted mean‡, §) | -0.5* | |
| Patients (%) achieving HbA1c <7% | 32 (14.3) | 12 (5.2) |
| FPG (mmol/L) | N=225 | N=229 |
| Baseline(mean) | 9.6 | 9.8 |
| Change from baseline(adjusted mean‡) | -1.2 | -0.2 |
| Difference from placebo (adjusted mean‡) | -1.0* |
| 2-hour PPG (mmol/L) | N=182 | N=189 |
|---|---|---|
| Baseline(mean) | 15.6 | 15.6 |
| Change from baseline(adjusted mean‡) | -2.2 | 0.1 |
| Difference from placebo (adjusted mean‡) | -2.2* | |
| Body Weight (kg)¶ | N=201 | N=200 |
| Baseline(mean) | 87.9 | 88.0 |
| Change from baseline(adjusted mean‡) | -0.1 | 0.0 |
| Difference from placebo (adjusted mean‡) | -0.1# |
† All Patients Treated Population (an intention-to-treat analysis).
‡ Least squares mean adjusted for insulin use at Visit 1 (premixed vs. non-pre-mixed [intermediate- or long-acting]), and baseline value.
§ Treatment by insulin stratum interaction was not significant (p>0.10).
* p<0.001 compared to placebo.
¶ All Patients as Treated (APaT) population, excluding data following glycemic rescue therapy.
# Not statistically significant (p≥0.05) compared to placebo.
Add-on Combination Therapy with Metformin plus Pioglitazone
Table 15 – Summary of Patient Demographics for Clinical Trials in Specific Indication
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
|---|---|---|---|---|---|
| P128 | Multicentre, randomized, double- blind, placebo- controlled | Sitagliptin 100 mg/day + Pioglitazone ≥30 mg/day + Metformin ≥1500 mg/day or Placebo + Pioglitazone ≥30 mg/day + Metformin ≥1500 mg/day Oral 26-week | 313 | 56.1 (22–78) | Male: 195 Female: 118 |
A total of 313 patients with type 2 diabetes participated in a 26-week, randomized, double-blind, placebo-controlled study designed to assess the efficacy of sitagliptin in combination with pioglitazone and metformin. Patients with inadequate glycemic control on a stable regimen of pioglitazone (30 or 45 mg per day) and metformin (≥1500 mg per day) were randomized to the addition of either 100 mg of sitagliptin or placebo, administered once daily.
In combination with pioglitazone and metformin, sitagliptin provided significant improvements in HbA1c, FPG, and 2-hour PPG compared to placebo with pioglitazone and metformin (Table 16). Lipid effects were generally neutral. The difference between sitagliptin and placebo in body weight change was not significant.
Table 16 – Glycemic Parameters and Body Weight at Final Visit (26-Week Study) for Sitagliptin as Add- on Combination Therapy with Pioglitazone and Metformin†
Sitagliptin 100 mg + Pioglitazone 30 or 45 mg + Metformin | Placebo + Pioglitazone 30 or 45 mg + Metformin | |
|---|---|---|
| HbA1c (%) | N=152 | N=153 |
| Baseline (mean) | 8.8 | 8.6 |
| Change from baseline(adjusted mean‡) | -1.2 | -0.4 |
| Difference from placebo (adjusted mean‡) | -0.7§ | |
| Patients (%) achieving HbA1c <7% | 38 (25.0) | 15 (9.8) |
| FPG (mmol/L) | N=155 | N=153 |
| Baseline(mean) | 10.0 | 9.6 |
| Change from baseline(adjusted mean‡) | -1.1 | -0.2 |
| Difference from placebo (adjusted mean‡) | -1.0§ | |
| 2-hour PPG (mmol/L) | N=141 | N=135 |
| Baseline(mean) | 15.3 | 14.7 |
| Change from baseline(adjusted mean‡) | -3.0 | -0.8 |
| Difference from placebo (adjusted mean‡) | -2.2§ | |
| Body Weight (kg)* | N=146 | N=128 |
| Baseline(mean) | 81.4 | 82.0 |
| Change from baseline(adjusted mean‡) | 1.3 | 1.1 |
| Difference from placebo (adjusted mean‡) | 0.1¶ |
† Full Analysis Set population (an intention-to-treat analysis).
‡ Least squares mean adjusted for baseline value.
§ p<0.001 compared to placebo.
* All Patients as Treated (APaT) population, excluding data following glycemic rescue therapy.
¶ Not statistically significant (p≥0.05) compared to placebo.
TECOS Cardiovascular Safety Study: The Trial Evaluating Cardiovascular Outcomes with Sitagliptin (TECOS) was a randomized, double-blind, placebo-controlled, parallel-group, event-driven, multicenter study in patients with type 2 diabetes mellitus (HbA1c ≥6.5 to 8.0%) and established vascular disease (coronary artery disease, ischemic cerebrovascular disease, atherosclerotic peripheral artery disease). The study included 14,671 patients (70.7% male, 29.3% female) in the intention-to-treat population who received sitagliptin (N=7,332) 100 mg daily (or 50 mg daily if the baseline eGFR was ≥30 and <50 mL/min/1.73 m2) or placebo (N=7,339) added to usual care targeting regional standards for HbA1c and CV risk factors. The median duration of treatment was 31 months and the median duration of follow-up was 36 months. Patients with an eGFR <30 mL/min/1.73 m2 were not to be enrolled in the study. The study population included 10,863 patients with coronary artery disease, 3,588 patients with cerebrovascular disease, 2,433 patients with peripheral artery disease, 2,643 patients with prior congestive heart failure (including 373 with New York Heart Association [NYHA] class 3 or higher), 2,004 patients ≥75 years of age and 3,324 patients with renal impairment (eGFR <60 mL/min/1.73 m2).
The primary cardiovascular endpoint was a composite of the first occurrence of cardiovascular death, non-fatal myocardial infarction, non-fatal stroke, or hospitalization for unstable angina. Secondary cardiovascular endpoints included a composite of the first occurrence of cardiovascular death, non-fatal myocardial infarction, or non-fatal stroke; as well as first occurrence of the following independent CV endpoints: cardiovascular death, myocardial infarction (fatal + non-fatal), stroke (fatal + non-fatal), hospitalization for unstable angina, hospitalization for heart failure, and all-cause mortality. A composite endpoint of first occurrence of death due to heart failure or hospitalization for congestive heart failure was also assessed.
Sitagliptin, when added to usual care, did not increase the risk of major adverse cardiovascular events or the risk of death or hospitalization for heart failure compared to usual care without sitagliptin patients with type 2 diabetes. Superiority to placebo was not demonstrated for any endpoint (Table 17).
Table 17 – Rates of Composite Cardiovascular Outcomes and Key Secondary Outcomes Censored at End of Follow-up (Intention-to-Treat Population)
| Sitagliptin (N=7,332) | Placebo N=7,339) | Hazard Ratio (95% CI) | p-value† | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Subjects with Events N (%) | Incidence Rate per 100 Patient- Years* | Subjects with Events N (%) | Incidence Rate per 100 Patient- Years* | ||||||||||
Primary Composite Endpoint (Cardiovascular death, non-fatal myocardial infarction, non-fatal stroke, or hospitalization for unstable angina) | 839 (11.4) | 4.1 | 851 (11.6) | 4.2 | 0.98 (0.89, 1.08) | <0.001 | |||||||
Secondary Composite Endpoint (Cardiovascular death, non-fatal myocardial infarction, or non-fatal stroke) | 745 (10.2) | 3.6 | 746 (10.2) | 3.6 | 0.99 (0.89, 1.10) | <0.001 | |||||||
| Secondary Outcome | |||||||||||||
| Cardiovascular death | 380 (5.2) | 1.7 | 366 (5.0) | 1.7 | 1.03 (0.89, 1.19) | 0.711 | |||||||
| All myocardial infarction (fatal and non-fatal) | 300 (4.1) | 1.4 | 316 (4.3) | 1.5 | 0.95 (0.81, 1.11) | 0.487 | |||||||
| All stroke(fatal and non-fatal) | 178 (2.4) | 0.8 | 183 (2.5) | 0.9 | 0.97 (0.79, 1.19) | 0.760 | |||||||
| Hospitalization for unstable angina | 116 (1.6) | 0.5 | 129 (1.8) | 0.6 | 0.90 (0.70, 1.16) | 0.419 | |||||||
| Death from any cause | 547 (7.5) | 2.5 | 537 (7.3) | 2.5 | 1.01 (0.90, 1.14) | 0.875 | |||||||
| Hospitalization for heart failure‡ | 228 (3.1) | 1.1 | 229 (3.1) | 1.1 | 1.00 (0.83, 1.20) | 0.983 | |||||||
| Death due to heart failure or hospitalization for heart failure‡ | 237 (3.2) | 1.1 | 240 (3.3) | 1.1 | 0.99 (0.83, 1.18) | 0.909 | |||||||
* Incidence rate per 100 patient-years is calculated as 100 × (total number of patients with ≥1 event during eligible exposure period per total patient-years of follow-up).
† Based on a Cox model stratified by region. For composite endpoints, the p-values correspond to a test of non- inferiority seeking to show that the hazard ratio is less than 1.3. For all other endpoints, the p-values correspond to a test of differences in hazard rates.
‡ The analysis of hospitalization for heart failure was adjusted for a history of heart failure at baseline.
Metformin hydrochloride
The prospective randomized (UKPDS) study has established the long-term benefit of intensive blood glucose control in adult patients with type 2 diabetes. Analysis of the results for overweight patients treated with metformin after failure of diet alone showed:
A significant reduction of the absolute risk of any diabetes-related complication in the metformin group (29.8 events/1000 patient-years) versus diet alone (43.3 events/1000 patient- years), p=0.0023, and versus the combined sulfonylurea and insulin monotherapy groups
(40.1 events/1000 patient-years), p=0.0034.
A significant reduction of the absolute risk of diabetes-related mortality: metformin
7.5 events/1000 patient-years, diet alone 12.7 events/1000 patient-years, p=0.017. There was no significant difference between the metformin group and those assigned intensive therapy with sulfonylurea or insulin.
A significant reduction of the absolute risk of overall mortality: metformin
13.5 events/1000 patient-years versus diet alone 20.6 events/1000 patient-years (p=0.011), and versus the combined sulfonylurea and insulin monotherapy groups 18.9 events/1000 patient-years (p=0.021).
A significant reduction in the absolute risk of myocardial infarction: metformin
11 events/1000 patient-years, diet alone 18 events/1000 patient-years (p=0.01). There was no significant difference between the metformin group and those assigned intensive therapy with sulfonylurea or insulin.
There were no significant differences between the metformin group and the diet alone in the other aggregate endpoints (stroke, peripheral vascular disease and microvascular complications).
14.2 Comparative Bioavailability Studies:
A randomized, two treatment, two period, single dose (1 x 50 mg/500 mg), crossover bioequivalence study of Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride (Auro Pharma Inc.) and JANUMET® (Merck Canada Inc.) was conducted in healthy, adult, human subjects under fasting conditions. A summary of the data from the 26 subjects that were included in the statistical analysis is presented in the tables below.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Sitagliptin (1 x 50 mg / 500 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 2113.28 2150.21 (18.9) | 2094.77 2131.13 (19.0) | 100.9 | 97.9 - 104.0 |
AUCI (ng•h/mL) | 2179.97 2219.32 (19.2) | 2163.91 2202.94 (19.4) | 100.7 | 97.7 - 103.9 |
Cmax (ng/mL) | 146.74 150.37 (22.7) | 148.47 151.75 (21.5) | 98.8 | 91.2 - 107.1 |
Tmax3 (h) | 4.84 (1.67 - 8.00) | 4.33 (1.67 - 10.00) | ||
T½4 (h) | 8.97 (10.1) | 9.25 (11.0) | ||
1 Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride (sitagliptin (as sitagliptin hydrochloride monohydrate) and metformin hydrochloride) tablets, 50 mg / 500 mg (Auro Pharma Inc.)
2 JANUMET (sitagliptin (as sitagliptin phosphate monohydrate) and metformin hydrochloride) tablets, 50 mg / 500 mg (Merck Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Metformin (1 x 50 mg / 500 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng•h/mL) | 10680.35 11114.86 (28.8) | 10393.09 10872.31 (30.3) | 102.8 | 97.0 - 108.9 |
AUCI (ng•h/mL) | 10752.53 11183.25 (28.6) | 10457.56 10931.18 (30.1) | 102.8 | 97.0 - 108.9 |
Cmax (ng/mL) | 1191.56 1229.92 (27.2) | 1118.83 1171.43 (30.4) | 106.5 | 97.6 - 116.2 |
Tmax3 (h) | 1.33 (0.75 - 7.00) | 1.67 (1.00 - 6.00) | ||
T½4 (h) | 4.52 (19.6) | 4.75 (16.9) | ||
1 Auro-Sitagliptin Hydrochloride and Metformin Hydrochloride (sitagliptin (as sitagliptin hydrochloride monohydrate) and metformin hydrochloride) tablets, 50 mg / 500 mg (Auro Pharma Inc.)
2 JANUMET (sitagliptin (as sitagliptin phosphate monohydrate) and metformin hydrochloride) tablets, 50 mg / 500 mg (Merck Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
No animal studies have been conducted with the combined products in sitagliptin and metformin hydrochloride to evaluate carcinogenesis, mutagenesis, impairment of fertility or effects on reproduction. The following data are based on the findings in studies with sitagliptin and metformin individually and a 16 week toxicity study in dogs with the concomitant administration of sitagliptin and metformin.
General Toxicology:
Acute Toxicity
Sitagliptin
The approximate LD50 of sitagliptin given orally to rats is >3000 mg/kg (maximum dose tested). This dose is equivalent to ≥200 times the human exposure based on the recommended daily adult human dose of 100 mg/day. In mice the approximate oral LD50 of sitagliptin is 4000 mg/kg. This dose is equivalent to >385 times the human exposure based on recommended daily adult human dose of 100 mg/day.
Chronic Toxicity
Sitagliptin and Metformin
Preclinical toxicokinetic and oral toxicity studies in dogs have been conducted with the combined products in sitagliptin and metformin hydrochloride.
In a sixteen-week oral toxicity study, female dogs were administered 20 mg/kg/day of metformin, alone or in combination with 2, 10, or 50 mg/kg/day of sitagliptin. Transient ataxia and/or tremors were observed in the high-dose combination-treatment group. These signs were considered to be an effect of sitagliptin because they were seen in previous dog studies with sitagliptin alone at 50 mg/kg/day. The no-effect level for treatment-related changes in this study was 10 mg/kg/day of sitagliptin plus 20 mg/kg/day of metformin, which provided systemic exposure to sitagliptin of approximately 6 times that in patients treated with 100 mg/day of sitagliptin and systemic exposure to metformin of approximately 2.5 times that in patients treated with 2000 mg/day of metformin.
Sitagliptin
The toxicity potential of sitagliptin was evaluated in a series of repeated dose toxicity studies of up to 53 weeks in dogs and up to 27 weeks in rats. In dogs administered sitagliptin orally at dosages of 2, 10 and 50 mg/kg/day, the no-observed effect level was 10 mg/kg/day (up to 6 times the human exposure based on the recommended daily adult human dose of 100 mg/day). Treatment-related physical signs observed in the 50 mg/kg/day group included open-mouth breathing, salivation, white foamy emesis, ataxia, trembling, decreased activity, and/or hunched posture. These signs were transient, slight in degree, and occurred with decreased incidence during the course of the study. In addition, very slight to slight skeletal muscle degeneration was observed histologically in the 14- and 27-week toxicity studies at the 50 mg/kg/day dose. However, no skeletal muscle degeneration was found in the 53-week toxicity study, indicating the lack of reproducibility or progression of this change with increased duration of treatment. The 50 mg/kg/day dose in dogs resulted in systemic exposure values 26 times the human exposure at the recommended daily adult human dose of 100 mg/day. In rats, sitagliptin administered orally at dosages of up to 180 mg/kg/day (up to 23 times the human exposure based on the recommended daily adult human dose of 100 mg/day), no significant toxicity was observed. The only drug-related effect observed was post-dose salivation, likely related to poor palatability of the drug, at doses of 60 mg/kg/day and 180 mg/kg/day.
The treatment-related changes noted in animals do not suggest any clinical concerns at the recommended therapeutic dosages in humans.
Carcinogenicity:
Sitagliptin
A two-year carcinogenicity study was conducted in male and female rats given oral doses of sitagliptin of 50, 150, and 500 mg/kg/day. There was an increased incidence of hepatic adenomas and carcinomas in the high-dose males and hepatic carcinomas in the high-dose females. This dose in rats results in approximately 58 times the human exposure based on the recommended daily adult human dose of 100 mg/day. This dose level was associated with hepatotoxicity in rats. The no-observed effect level for induction of hepatic neoplasia was 150 mg/kg/day, approximately 19-fold the human exposure at the 100-mg recommended dose. Since hepatotoxicity has been shown to correlate with induction of hepatic neoplasia in rats, this increased incidence of hepatic tumors in rats was likely secondary to chronic hepatic toxicity at this high dose. The clinical significance of these findings for humans is unknown.
A two-year carcinogenicity study was conducted in male and female mice at oral doses of 50, 125, 250, and 500 mg/kg/day. Sitagliptin did not increase tumor incidence in mice in any organ at doses up to 500 mg/kg/day (approximately 68 times the human exposure based on the recommended daily adult human dose of 100 mg/day).
Metformin hydrochloride
Long-term carcinogenicity studies have been performed in rats (dosing duration of 104 weeks) and mice (dosing duration of 91 weeks) at doses up to and including 900 mg/kg/day and 1500 mg/kg/day, respectively. These doses are both approximately three times the maximum recommended human daily dose based on body surface area comparisons. No evidence of carcinogenicity with metformin was found in either male or female mice. Similarly, there was no tumorigenic potential observed with metformin in male rats. There was, however, an increased incidence of benign stromal uterine polyps in female rats treated with 900 mg/kg/day.
A carcinogenicity study was also conducted via dermal administration in Tg.AC transgenic mice at doses up to and including 2000 mg/kg/day. No evidence of carcinogenicity was observed in either male or female mice.
Genotoxicity:
Sitagliptin
Sitagliptin was not mutagenic or clastogenic in a battery of genetic toxicology studies, including the Ames bacterial assay (microbial mutagenesis test), Chinese hamster ovary cells (CHO cells) chromosome aberration assay, an in vitro cytogenetics assay using CHO cells, an in vitro rat hepatocyte DNA alkaline elution assay (an assay which measures the compound’s ability to induce single strand breaks in DNA), and an in vivo micronucleus assay.
Metformin hydrochloride
There was no evidence of a mutagenic potential of metformin in the following in vitro tests: Ames test (S. typhimurium), gene mutation test (mouse lymphoma cells), or chromosomal aberrations test (human lymphocytes). Results in the in vivo mouse micronucleus test were also negative.
Reproductive and Developmental Toxicology:
No animal studies have been conducted with the combined products in sitagliptin and metformin hydrochloride to evaluate effects on reproduction. The following data are based on findings in studies performed with sitagliptin or metformin individually.
Sitagliptin
No adverse effects upon fertility were observed in male and female rats given sitagliptin orally at doses up to 1000 mg/kg daily (up to approximately 100 times the human exposure based on the recommended daily adult human dose of 100 mg/day) prior to and throughout mating.
Sitagliptin was not teratogenic in rats at oral doses up to 250 mg/kg or in rabbits given up to 125 mg/kg during organogenesis (up to 32 and 22 times the human exposure based on the recommended daily adult human dose of 100 mg/day). A slight, treatment-related increased incidence of fetal rib malformations (absent, hypoplastic and wavy ribs) was observed in the offspring of rats at oral doses of 1000 mg/kg/day (approximately 100 times the human exposure based on the recommended daily adult human dose of 100 mg/day). The no-observed effect level for developmental effects was 250 mg/kg/day (32 times the human exposure based on the recommended daily adult human dose of 100 mg/day).
Treatment-related decreases in the mean preweaning body weight of both sexes and postweaning body weight gain of male animals was observed in offspring of rats at oral doses of 1000 mg/kg.
Metformin hydrochloride
Fertility of male or female rats was unaffected by metformin when administered at doses as high as 600 mg/kg/day, which is approximately three times the maximum recommended human daily dose based on body surface area comparisons.
A decrease in male reproductive organ weights was observed at higher oral dose of 900 mg/kg/day in a fertility and developmental toxicity study in rats.
Metformin was not teratogenic in rats and rabbits at doses up to 600 mg/kg/day. This represents an exposure of about 2 times the maximum recommended human daily dose based on body surface area comparisons. Determination of fetal concentrations demonstrated a partial placental barrier to metformin.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. JANUMET (Sitagliptin (as sitagliptin phosphate monohydrate) and metformin hydrochloride tablets 50 mg/500 mg, 50 mg/850 mg and 50 mg/1000 mg, Oral), Submission Control No. 242894, Product Monograph, Merck Canada Inc. July 27, 2021.