


Product Monograph - Betoptic S
INDICATIONS
For lowering intraocular pressure in the treatment of ocular hypertension or chronic open angle glaucoma. May be used alone or in combination with other IOP-lowering medication.
CONTRAINDICATIONS
- Hypersensitivity to the active substance (substances), or to any of the excipients.
- Reactive airway disease including bronchial asthma or a history of bronchial asthma, severe chronic obstructive pulmonary disease.
- Sinus bradycardia, sick sinus syndrome sino-atrial block, second or third degree atrioventricular block not controlled with pace-maker. Overt cardiac failure, cardiogenic shock.
PRECAUTIONS
General:
Like other topically applied ophthalmic agents, betaxolol is absorbed systemically. Due to the beta-adrenergic component, betaxolol, the same types of cardiovascular, pulmonary and other adverse reactions seen with systemic beta-adrenergic blocking agents may occur. Incidence of systemic ADRs after topical ophthalmic administration is lower than for systemic administration. To reduce the systemic absorption (see DOSAGE AND ADMINISTRATION section).
Although ophthalmic betaxolol has demonstrated a low potential for systemic effects, it should be used with caution in patients with bradycardia, and those with diabetes (especially labile diabetes) because of possible masking of hypoglycemia. Consideration should be given to the gradual withdrawal of all beta-adrenergic blocking agents in patients suspected of developing thyrotoxicosis, and also prior to general anesthesia, because of the reduced ability of the heart to respond to beta-adrenergically mediated sympathetic reflex stimuli (see DRUG INTERACTIONS).
Betaxolol, a cardioselective beta-blocker, has produced only minimal effects in patients with reactive airway disease; however, caution should be exercised in the treatment of patients with excessive restriction of pulmonary function.
In patients with angle-closure glaucoma, the immediate treatment objective is to reopen the angle by constriction of the pupil with a miotic agent. Betaxolol HCl has no effect on the pupil; therefore, ophthalmic betaxolol should be used with a miotic to reduce elevated intraocular pressure in angle-closure glaucoma.
As with the use of other antiglaucoma drugs, diminished responsiveness to ophthalmic betaxolol after prolonged therapy has been reported in some patients. However, in one long-term study in which 250 patients treated with betaxolol ophthalmic solution have been followed for up to three years, no significant difference in mean intraocular pressure has been observed after initial stabilization.
Cardiac disorders:
In patients with cardiovascular diseases (e.g. coronary heart disease, Prinzmetal’s angina and cardiac failure) and hypotension therapy with beta-blockers should be critically assessed and the therapy with other active substances should be considered. Patients with cardiovascular diseases should be watched for signs of deterioration of these diseases and of adverse reactions. Due to its negative effect on conduction time, beta-blockers should only be given with caution to patients with first degree heart block.
Vascular disorders:
Patients with severe peripheral circulatory disturbance/disorders (i.e. severe forms of Raynaud’s disease or Raynaud’s syndrome) should be treated with caution.
Respiratory disorders:
Respiratory reactions, including death due to bronchospasm in patients with asthma have been reported following administration of some ophthalmic beta-blockers.
Patients with mild/moderate bronchial asthma, a history of mild/moderate chronic obstructive pulmonary disease (COPD) should be treated with caution.
Hypoglycemia/diabetes:
Beta-blockers should be administered with caution in patients subject to spontaneous hypoglycemia or to patients with labile diabetes, as beta-blockers may mask the signs and symptoms of acute hypoglycemia.
Hyperthyroidism:
Beta-blockers may also mask the signs of hyperthyroidism.
Corneal diseases:
Ophthalmic β-blockers may induce dryness of eyes. Patients with corneal diseases should be treated with caution.
Other beta-blocking agents:
The effect on intra-ocular on pressure or the known effects of systemic beta-blockade may be potentiated when betaxolol is given to the patients already receiving a systemic beta-blocking agent. The response of these patients should be closely observed. The use of two topical beta-adrenergic blocking agents is not recommended.
Muscle Weakness
Beta-adrenergic blocking agents have been reported to potentiate muscle weakness consistent with certain myasthenic symptoms (e.g. diplopia, ptosis and generalized weakness).
Anaphylactic reactions:
While taking beta-blockers, patients with history of atopy or a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated challenge with such allergens and unresponsive to the usual dose of adrenaline used to treat anaphylactic reactions.
Choroidal detachment:
Choroidal detachment has been reported with administration of aqueous suppressant therapy (e.g. timolol, acetazolamide) after filtration procedures.
Surgical anaesthesia:
β-blocking ophthalmological preparations may block systemic β-agonist effects e.g. adrenaline. The anaesthesiologist should be informed when the patient is receiving betaxolol.
Contact lenses:
Betoptic* S® contains benzalkonium chloride which may cause irritation and is known to discolour soft contact lenses. Avoid contact with soft contact lenses. Patients must be instructed to remove contact lenses prior to application of BETOPTIC* S and wait at least 15 minutes before reinsertion.
Drug Interactions:
No specific drug interaction studies have been performed with betaxolol. There is a potential for additive effects resulting in hypotension and/or marked bradycardia when ophthalmic beta-blockers solution is administered concomitantly with oral calcium channel blockers, beta-adrenergic blocking agents, antiarrhythmics (including amiodarone), digitalis glycosides, parasympathomimetics, guanethidine.
Beta blockers can decrease the response to adrenaline used to treat anaphylactic reactions. Special caution should be exercised in patients with a history of atopy or anaphylaxis.
Mydriasis resulting from concomitant use of ophthalmic beta-blockers and adrenaline (epinephrine) has been reported occasionally.
Close observation of the patient is recommended when a beta-blocker is administered to patients receiving oral beta-adrenergic blocking drugs, or catecholamine-depleting drugs such as reserpine, because of possible additive effects. Caution should be exercised in patients using concomitant adrenergic psychotropic drugs.
Fertility
There are no data on the effects of BETOPTIC* S on human fertility.
Pregnancy:
There are no adequate data for the use of betaxolol in pregnant women. Betaxolol should not be used during pregnancy unless clearly necessary. To reduce systemic absorption (see DOSAGE AND ADMINISTRATION section). Epidemiological studies have revealed malformative effects but show a risk for intra uterine growth retardation when beta-blockers are administered by the oral route. In addition signs and symptoms of beta-blockade (e.g. bradycardia, hypotension, respiratory distress and hypoglycemia) have been administered until delivery. If BETOPTIC* S is administered until delivered until delivery, the neonate should be carefully monitored during the first day of life.
Nursing Mothers:
Beta-blockers are excreted in breast milk. However, at therapeutic doses of betaxolol in eye drops it is not likely that sufficient amounts would be present in breast milk to produce clinical symptoms of beta-blockade in the infant. To reduce systemic absorption (see DOSAGE AND ADMINISTRATION section).
Usage in Children:
Clinical studies to establish the safety and efficacy in children have not been performed.
Effects on ability to drive and use machines:
Temporary blurred vision or other visual disturbances may affect the ability to drive or use machines. If blurred vision occurs after instillation, the patient must wait until the vision clears before driving or using machinery.
ADVERSE REACTIONS
The following adverse reactions have been reported in clinical trials of up to three years of patient experience with BETOPTIC* S (Betaxolol Hydrochloride Ophthalmic Suspension).
Ocular:
BETOPTIC* S has been well tolerated. Ocular discomfort of short duration has been experienced by some patients upon instillation and increased tearing has been reported. Instances of blurred vision on instillation, decreased corneal sensitivity, erythema, itching sensation, corneal punctate staining, keratitis, anisocoria and photophobia have been reported.
Systemic:
Systemic reactions following topical administration of BETOPTIC* S have been reported rarely (e.g., CNS: insomnia and depressive neurosis). Common occurrence of headache has been reported.
Like other topically applied ophthalmic drugs, betaxolol is absorbed into systemic circulation. This may cause similar undesirable effects as seen with systemic beta-blocking agents. Incidence of systemic ADRs after topical ophthalmic administration is lower than for systemic administration. Listed adverse reactions include reactions seen within the class of ophthalmic beta-blockers.
Additional adverse reactions have been seen with ophthalmic beta-blockers and may potentially occur with BETOPTIC* S.
Immune system disorders:
Systemic allergic reactions including angioedema, urticaria, localized and generalized rash, pruritus, anaphylactic reaction.
Metabolism and nutrition disorders:
Hypoglycemia.
Psychiatric disorders:
Insomnia, depression, nightmares, memory loss.
Nervous system disorders:
Syncope, cerebrovascular accident, cerebral ischemia, increases in signs and symptoms of myasthenia gravis, dizziness, paraesthesia, and headache.
Eye disorders:
Signs and symptoms of ocular irritation (e.g. burning, stinging, itching, tearing, redness), blepharitis, keratitis, blurred vision and choroidal detachment following filtration surgery, decreased corneal sensitivity, dry eyes, corneal erosion, ptosis, diplopia.
Cardiac disorders:
Bradycardia, chest pain, palpitations, edema, arrhythmia, congestive heart failure, atrioventricular block, cardiac arrest, cardiac failure.
Vascular disorders:
Hypotension, Raynaud’s phenomenon, cold hands and feet.
Respiratory, thoracic, and mediastinal disorders:
Bronchospasm (predominantly in patients with pre-existing bronchospastic disease), dyspnoea, cough.
Gastrointestinal disorders:
Dysgeusia, nausea, dyspepsia, diarrhea, dry mouth, abdominal pain, vomiting.
Skin and subcutaneous tissue disorders:
Alopecia, psoriasiform rash or exacerbation of psoriasis, skin rash.
Musculoskeletal and connective tissue disorders:
Myalgia
Reproductive system and breast disorders:
Sexual dysfunction, decreased libido.
General disorders and administration site conditions:
Asthenia/fatigue.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
SYMPTOMS:
No data are available on overdosage of humans. However, anticipated symptoms include symptomatic bradycardia, hypotension, bronchospasm, acute cardiac failure and heart block (second or third degree).
A 10 mL container of 0.25% BETOPTIC* S would contain 25 mg of betaxolol. Betaxolol HCl at 40 mg
BID is reported to be an effective and safe systemic dosage for hypertension. Thus, an individual would ingest an amount of betaxolol from one container which is less than the maximum daily oral dose of betaxolol HCl.
Since the oral LD50 in animals ranged from 350 to 1,050 mg/kg, a 10kg child would only receive 2.5 mg/kg if the child ingested 10 mL of 0.25% BETOPTIC* S. An acute toxic response is thus extremely remote.
TREATMENT:
| For management of a suspected drug overdose, particularly accidental oral ingestion, contact your regional poison control centre immediately. |
Should an overdosage occur the following is suggested:
Ocular: Flush eye with lukewarm tap water.
Systemic:
- Gastric lavage.
- Symptomatic bradycardia: use atropine sulfate intravenously in a dosage of 0.25 mg to 2 mg to induce vagal blockage. If bradycardia persists, intravenous isoproterenol hydrochloride should be administered cautiously. In refractory cases the use of a transvenous cardiac pacemaker may be considered.
- Hypotension: use sympathomimetic pressor drug therapy, such as dopamine, dobutamine or levarterenol. In refractory cases, the use of glucagon hydrochloride has been reported to be useful.
- Bronchospasm: use isoproterenol hydrochloride. Additional therapy with aminophylline may be considered.
- Acute cardiac failure: conventional therapy with digitalis, diuretics, and oxygen should be instituted immediately. In refractory cases the use of intravenous aminophylline is suggested. This may be followed, if necessary, by glucagon hydrochloride which has been reported to be useful.
- Heart block (second or third degree): use isoproterenol hydrochloride or a transvenous cardiac pacemaker.
DOSAGE AND ADMINISTRATION
The usual dose is one drop of BETOPTIC* S (Betaxolol Hydrochloride Ophthalmic Suspension) in the affected eye(s) twice daily. When using nasolacrimal occlusion or closing the eyelids for 2 minutes, the systemic absorption is reduced. This may result in a decrease in systemic side effects and an increase in local activity. In some patients, the intraocular pressure lowering response may require a few weeks to stabilize. Clinical follow-up should include a determination of the intraocular pressure during the first month of treatment. Thereafter, intraocular pressures should be determined on an individual basis at the judgment of the physician.
When a patient is transferred from a single antiglaucoma agent, continue the agent already used and add one drop of BETOPTIC* S in the affected eye(s) twice a day. On the following day, discontinue the previous antiglaucoma agent completely and continue with BETOPTIC* S.
Because of diurnal variation of intraocular pressure in individual patients, satisfactory response to twice a day therapy is best determined by measuring intraocular pressure at different times during the day. Intraocular pressure of less than 22 mm Hg may not be optimal for control of glaucoma in each patient; therefore, therapy should be individualized.
If the intraocular pressure of the patient is not adequately controlled on this regimen, concomitant therapy with pilocarpine, other miotics, epinephrine or systemically administered carbonic anhydrase inhibitors can be instituted.
When a patient is transferred from several concomitantly administered anti-glaucoma agents, individualization is required. Adjustment should involve one agent at a time made at intervals of not less than one week. A recommended approach is to continue the agents being used and add one drop of BETOPTIC* S in the affected eye(s) twice a day. On the following day, discontinue one of the other antiglaucoma agents. The remaining antiglaucoma agents may be decreased or discontinued according to the patient’s response to treatment. The physician may be able to discontinue some or all of the other antiglaucoma agents.
PHARMACEUTICAL INFORMATION
Drug Substance:
Chemical Name: (+)-1-[p-[2-(Cyclopropylmethoxy)ethyl]phenoxy]-3-(isopropylamino)-2-propanol hydrochloride.
Structural Formula:
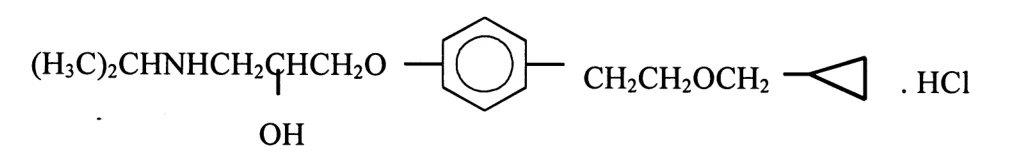
Betaxolol Hydrochloride
MW: 343.89
Physical Form: White crystalline powder.
Solubility: Approximately 35% in water
pKa: 9.34
pH: At pH 7.4, approximately 98.9% of the compound in the formulation is ionized.
Partition Coefficient: 3.5 (octanol: water)
Permeability Coefficient: 3.5 x 10⁻⁵ cm/sec.
Melting Point: About 114°C
Composition:
BETOPTIC* S (Betaxolol Hydrochloride Ophthalmic Suspension) is a sterile isotonic aqueous suspension containing betaxolol 0.25% w/v (0.28% w/v betaxolol hydrochloride) with benzalkonium chloride (as preservative), mannitol, poly (styrene-divinyl benzene) sulfonic acid, carbomer 934P, edetate disodium, hydrochloric acid and/or sodium hydroxide (to adjust pH) and purified water.
Stability and Storage Recommendations:
Store at room temperature (15 – 30°C).
Special Instructions:
Patients should be instructed to avoid contamination of the dropper tip.
BETOPTIC* S Suspension must be well shaken before use. Store the bottle in the outer container.
AVAILABILITY
PrBETOPTIC* S Suspension is supplied in plastic ophthalmic Drop-tainer® dispensers containing 5 mL, and 10 mL.
ANIMAL PHARMACOLOGY
The adrenergic receptors associated with mydriasis in man and the other mammalian species are classified as of the alpha type. Thus, it is not to be expected that beta-blockers cause a significant change in pupil size. The pupillary activity of betaxolol HCl was studied in albino rabbits by instilling drops of solutions containing 0, 0.125%, 0.25%, 0.5%, or 1.0% betaxolol HCl, or 0.5% proparacaine into the cul-de-sac and measuring the pupillary diameter before and at 3 hours after treatment. No change in pupil size was seen.
The peripheral vasorelaxing action of betaxolol has been shown in an in vivo study in dogs, while the vasorelaxing and calcium channel blocking actions of betaxolol have been demonstrated in several in vitro studies utilizing both non-ocular and ocular vessels from rat, guinea pig, rabbit, canine, porcine and bovine models. Betaxolol's action as a neuroprotective agent has been shown in both in vivo and in vitro experiments in rabbit retina, rat cortical cultures and chick retinal cultures.
Pharmacokinetics:
The ocular bioavailability of (3H[G])-RS-betaxolol HCl (0.5% ophthalmic solution) has been evaluated after administration of a 50 microliter dose in the eyes of healthy New Zealand albino rabbits. Six rabbits were used at each time interval of 5, 15, 30, 45, 60, 120, 240 and 360 minutes. One rabbit was dosed with its own positive nonradioactive control, and one rabbit was also dosed with its respective vehicle control. At the prescribed time, each rabbit was sacrificed, and samples were taken of the aqueous humor, cornea, iris and lens tissues, using appropriate techniques. The following results were obtained for Peak Time (TPc) and Peak Concentrations (Pc) in the tissues.
TPc (hours) Pc
Aqueous humor 0.5 7.16 ug/ml
Cornea 0.5 178.45 ug/g
Iris-ciliary body 0.75 12.17 ug/g
Lens 0.5 0.86 ug/g
Due to the high lipophilicity of this compound and the rapid permeation into corneal tissue, it appears possible that the rapid deequilibration/equilibration at the corneal surface allows high concentrations of the drug to enter the ocular tissue.
It is unclear whether the tissue kinetics of betaxolol from BETOPTIC* S suspension are similar to those of the solution.
CLINICAL PHARMACOLOGY
Glaucoma is the name of a group of diseases characterized by an elevated intraocular pressure (IOP) associated with optic nerve head damage and with consequent loss of visual field. On a statistical basis, the prognosis for the preservation of visual field in an eye with elevated IOP is inversely related to the level of IOP sustained by that eye. Thus, to improve the chances for slowing the progressive loss of visual field, a goal of glaucoma therapy is to reduce the IOP to a level within a range tolerated by the eye. Present medical therapy of glaucoma involves reduction of IOP by any of a wide variety of drugs.
The mechanism of ocular hypotensive action of betaxolol in eyes with normal or elevated IOP appears to be reduction of aqueous humor production, as demonstrated by tonography and aqueous fluorophotometry. The onset of action when used as a solution can generally be noted within 30 minutes and the maximal effect can usually be detected two hours after topical administration. Although the time of onset of action and the time of maximal effect for the suspension have not been determined, studies in rabbits indicate that the concentration of betaxolol in the aqueous humour appears to increase at the same rate following instillation of either the solution or the suspension. A single dose provides a 12-hour reduction in intraocular pressure. Clinical observation of glaucoma patients treated with ophthalmic betaxolol solution for up to three years shows that the intraocular pressure lowering effect is well maintained.
Clinical studies show that topical betaxolol solution reduces mean intraocular pressure 25% from baseline. In trials using 22 mm Hg as a generally accepted index of intraocular pressure control, ophthalmic betaxolol solution was effective in more than 94% of the population studied, of whom 73% were treated with the beta-blocker alone. In controlled, double-masked studies, the magnitude and duration of ocular hypotensive effect of ophthalmic betaxolol solution and ophthalmic timolol solution were clinically equivalent.
In controlled double masked studies, the magnitude and duration of the ocular hypotensive effect of betaxolol 0.5% solution and BETOPTIC* S 0.25% suspension were clinically equivalent. Patients treated with BETOPTIC* S Suspension (1.9%) reported ocular stinging and burning significantly less often than those patients treated with betaxolol solution (4.6%). However, transient blurred vision (a few seconds to a few minutes) was reported more often with BETOPTIC* S Suspension (3.3% vs 0.8%).
In addition to elevated intraocular pressure, clinical evidence indicates that vascular factors may also be risk factors in the progression of glaucoma and that vascular insufficiency to the optic nerve head or ganglion cell axons may result in glaucomatous visual field loss. During therapy with betaxolol, no negative effect on the blood supply to the optic nerve has been observed. Rather, betaxolol maintains or improves ocular blood flow/perfusion. Moreover, clinical data obtained during controlled clinical trials in patients with chronic open-angle glaucoma and ocular hypertension indicate that treatment with betaxolol has a long term benefit on the visual field.
Ophthalmic betaxolol solution has also been used successfully in glaucoma patients who have undergone a laser trabeculoplasty and have needed additional long-term ocular hypotensive therapy. It has been well-tolerated in glaucoma patients wearing hard or soft contact lenses and in aphakic patients. It has not been determined whether or not BETOPTIC* S Suspension can be used in these patients.
Ophthalmic betaxolol does not produce miosis or accommodative spasm which are frequently seen with miotic agents. The blurred vision and night blindness often associated with standard miotic therapy are not associated with ophthalmic betaxolol. Thus, patients with central lenticular opacities avoid the visual impairment caused by a constricted pupil.
The mode of action of beta-blockers in reducing IOP has not been fully elucidated; however, available studies indicate the decrease in IOP results from a reduction in the rate of formation of aqueous humor.
Cardioselectivity, intrinsic sympathomimetic activity and membrane stabilizing activity, properties that have been used to classify beta-blockers into several categories, do not appear to be major determinants of the IOP-reducing activity of these drugs judging from the published results of clinical trials with them. However, the degree to which such ancillary properties are possessed will influence the degree to which side effects will occur. Nonselective beta-blockers at ophthalmic doses cause a significant incidence of systemic side effects, particularly cardiopulmonary effects. Consequently, non-selective beta-blockers are contraindicated in patients with pulmonary disease. In contrast, a cardioselective beta-blocker should be less apt to produce bronchoconstriction, and this has been confirmed in studies in patients with reactive airway disease using either ophthalmic or oral doses of betaxolol.
Both bradycardia and bronchospasm have been reported to occur with topical ocular use of timolol, which is a non-selective beta-blocker without intrinsic sympathomimetic activity. Betaxolol HCl is a new cardioselective beta-blocker lacking intrinsic sympathomimetic activity with very weak local anesthestic properties.
Ophthalmic betaxolol solution (one drop in each eye) at twice the therapeutic dosage was compared to timolol and placebo in a three-way masked crossover study challenging patient reactive airway disease. Betaxolol HCl at twice the clinical concentration had no significant effect on pulmonary function as measure by Forced Expiratory Volume in one second (FEV1), Forced Vital Capacity (FVC) and FEV1/FVC. Additionally, the action of isoproterenol, a beta stimulant, administered at the end of the study was not inhibited by ophthalmic betaxolol HCl.
In contrast, ophthalmic timolol significantly decreased these pulmonary functions; the measurements subsequent to baseline were significantly (p<0.05) different from betaxolol HCl and placebo. Additionally, the action of isoproterenol, a beta-adrenergic stimulant, administered at the end of the study, was inhibited by timolol but not by betaxolol.
FEV1 - PERCENT CHANGE FROM BASELINE
Means
Betaxolol 1.0% Timolol 0.5% Placebo
solution solution
Baseline 1.6 1.4 1.4
60 Minutes 2.3 -25.7** 5.8
120 Minutes 1.6 -27.4** 7.5
240 Minutes -6.4 -26.9** 6.9
Isoproterenol 36.1 -12.4** 42.8
** Statistically significant (P < 0.05). Isoproterenol was inhaled at 240 minutes, and FEV1 was measured at 270 minutes after inhalation.
Paradoxically, despite its cardioselective action, ophthalmic doses of betaxolol have no significant effect on heart rate. Ophthalmic betaxolol solution (one drop in each eye) at twice the clinical concentration (1%) was compared to timolol (0.5%) solution and placebo in a double-masked three-way crossover study in 24 normal subjects comparing ophthalmic betaxolol HCl, timolol and placebo for effects on blood pressure and heart rate. Mean arterial blood pressure was not affected by any treatment; however, ophthalmic timolol produced a significant decrease in the mean heart rate. The mean heart rate for timolol at 4, 6, 8 and 10 minutes was significantly (p < 0.05) lower than betaxolol HCl or placebo.
MEAN HEART RATES
TREATMENT
Bruce Stress Exercise Test
Minutes Betaxolol 1% Timolol 0.5% Placebo solution solution
0 79.2 79.3 81.2
2 130.2 126.0 130.4
4 133.4 128.0*** 134.3
6 136.4 129.2*** 137.9
8 139.8 131.8*** 139.4
10 140.8 131.8*** 141.3
***Mean pulse rate significantly lower for timolol than betaxolol HCl or
placebo ( p < 0.05).
This study confirms that ophthalmic doses of betaxolol do not produce pharmacologically active tissue levels of the drug. Reported values for the volume of distribution of betaxolol in man range from 4.9 L/kg to 8.8 L/kg. Thus, even with complete systemic absorption of ophthalmic doses of betaxolol the concentrations of drug in body tissue will be significantly below the threshold concentration of approximately 5 ng/ml. The lack of effect of betaxolol on heart rate has been confirmed in long-term clinical trials in patients with glaucoma or ocular hypertension.
Pharmacokinetics:
Betaxolol is extensively absorbed from the gastrointestinal tract following oral administration, with peak plasma levels in 2 to 4 hours and an elimination half-life of 14-22 hours. The volume of distribution of betaxolol in man is 4.9 to 8.8 L/kg, the latter figures reported following repeated oral dosage. Betaxolol is not extensively bound to plasma protein and is excreted primarily in the urine. Although betaxolol is absorbed following ocular administration, threshold levels for systemic effects are not reached.
The fate of the resin contained in the betaxolol suspension, following topical application to the eye, is unknown. The reason for the inability to address this issue is that the resin is not soluble in water or organic solvents and the resin has resisted all attempts to radioactively label it.
TOXICOLOGY
Acute Toxicity
Species/Route LD50(mg/kg) Signs of Toxicity
Mouse, p.o. 482.7 All deaths occurred within one
(377.2 - 617.5) hour in dose/response manner.
Mouse, i.v. 42.6 All deaths occurred within one
(39.5 - 46.0) hour in dose/response manner.
Mouse, p.o. 920 (601-1408) Deaths 3 min - 5 hrs.
after lethal oral dose.
Mouse, i.v. 38 (32 - 44) Deaths occurred within 0.5 - 2 minutes after lethal i.v. dose;
Rat, p.o. 1050 (946 - 1166) Reduced motor activity
Rat, i.v. 39 (33 - 46) Ptosis and occasional convulsions.
Mouse, p.o. 350±23 (m) Difficulties in movement, tremors,
400±30 (f) stereotype behavior, clonic convulsions. Death 2-3 min.
after lethal dose.
Mouse, i.v. 40 ± 1.5 (m) Tremors, convulsive jumps,
55 ± 2.0 (f) clonic convulsions. Death
1-2 min. after lethal dose.
Rat, p.o. 980 ± 95 (m) Difficulties in movement,
860 ± 113 (f) tremors, stereotype behavior, hypersalivation, piloerection, cyanosis. Deaths within 24 hours.
Rat, i.v. 28 ± 1.6 (m) Tremors and clonic
25 ± 1.5 (f) convulsions; deaths within 10 min. in dose-related manner.
Subacute Toxicity
Species/Route Dosage Signs of Toxicity
(mg/kg/day)
Rat, i.v. 2, 6, 15 Unsteady gait after dosing, tremor, irregular
4 weeks breathing, piloerection, half-closed eyes, tail rigidity at 15 mg/kg. Reduced body weight gain and food consumption in male rats at
15 mg/kg .
Dog, i.v. 1, 3, 6 Ataxia, salivation, subduedness,
4 weeks high-stepping gait at 6mg/kg during first two weeks of dosing. Reduction in heart rate at
6 mg/kg after three weeks.
Rat, p.o. 25, 50, 100 (m) Slight increase in blood glucose
4 weeks 50, 100, 200 (f) and serum urea at 50 mg/kg; moderate increase in serum triglyceride at 100 mg/kg
(m) slight proteinuria at 100 and 200 mg/kg (f).
Rat, p.o. 100, 400 Hypersalivation at 100, 400 mg/kg;
13 weeks (f) prostration at 400 mg/kg. One mortality at
400 mg/kg. Increases in serum urea and creatinine levels at both dose levels. Slight hypertrophy of adrenal glands.
Rabbit, p.o. 30, 100 At 100 mg/kg, lower rate of body
4 weeks (f) weight gain, moderate increase in neutrophils and slight increase in serum globulin.
Mouse, p.o. 300, 400, 600 Higher incidence of poor coat
4 weeks condition at 400 and 600 mg/kg; dose-related reduction in weight gain at all dose levels.
Chronic Toxicity:
Species/Route Dosage Signs of Toxicity
(mg/kg/day)
Rat, p.o. 1.2, 2.5, 25, 400 Intermittent salivation, hair loss, reduced
26 weeks food and water intake at 1.5, 2.5 and 25mg/kg.
At 400 mg/kg, 20% mortality, salivation, tremors, unsteady gait, slight hair loss, lower body weight gain, elevated serum enzymes, elevated liver, adrenal and kidney weights. Minor histopathological changes at 400 mg/kg.
Rat, p.o. 6, 25, 100 Reduced overall body weight gain
61 weeks at 100 mg/kg and at 25 mg/kg (males). Slightly increased relative adrenal weights at 100 mg/kg
(males), and at 25 mg/kg and 100 mg/kg (females).
Dog, p.o. 2, 6, 20 Isolated instances of convulsions at 6 mg/kg
26 weeks and 20 mg/kg. Occasional head-nodding movements, vomiting and salivation at 20 mg/kg.
Significant reduction in heart rate after 6 and 24 weeks
(2, 6 mg/kg) and after 6, 12 and 24 weeks at 20 mg/kg.
Dog, p.o. 2, 6, 20 Head nodding movements, high-stepping gait,
52 weeks occasional vomiting and whining after dosing at 6 and
20 mg/kg. Slight decrease in systolic pressure at 6 and
20 mg/kg; possible bradycardia at 20 mg/kg.
Carcinogenicity:
Species/Route Dosage Signs of Toxicity
(mg/kg/day)
Mouse, p.o. 6, 20, 60 Reduced weight gain at 60 mg/kg.
102 weeks No evidence of carcinogenicity.
Rat, p.o. 3, 12, 48 Marked reduction in body weight gain
104 weeks at 48 mg/kg. No evidence of carcinogenicity.
Mutagenicity:
Test System Results
Ames Salmonella/Microsome Plate Test Negative
Mouse Lymphoma Forward Mutation Assay Negative
SCE and Chromosome Aberration Assay Negative
In-Vivo Malignant Transformation Assay Negative
Ames Metabolic Activation Test Negative
Micronucleus Test Negative
Reproduction and Teratology
Species/Route Dosage Findings
(mg/kg/day)
Rat, p.o. 4, 32, 256 Minimal effects at 4 and 32 mg/kg;
Fertility & General maternal and fetal toxicity at 256 mg/kg.
Reproductive Performance
Rat, p.o. 4, 32, 256 Minimal effects at 4 and 32 mg/kg;
Pre-and Post-Natal pronounced effects at 256 mg/kg.
Development
Rat, p.o. 100, 200, 400 Embryotoxic effects at 200 and 400 mg/kg.
Fetal Toxicity Total fetal resorption at 400 mg/kg.
and Teratogenicity
Rat, p.o. 4, 40, 400 No significant adverse effects at 4
Fetal Toxicity and 40 mg/kg. Maternal and fetal toxicity and Teratogenicity at 400 mg/kg.
Rabbit, p.o. 1, 4, 12, 36 No adverse effects on organogenesis
Fetal Toxicity at 1, 4 or 12 mg/kg. Reduced post- and Teratogenicity implantation survival at 36 mg/kg, but no adverse effects on morphogenesis.
Miscellaneous Studies
Species/Route Dosage Findings
(mg/kg/day)
Rabbit-Ocular 1.5 - 6 mg Moderate conjunctival congestion and
Irritation discharge, minimal cloudiness at 6 hours;
(1 day) minimal conjunctival congestion at 24 hours.
15 mg Severe conjunctival congestion and discharge, minimal swelling, flare, iritis, corneal cloudiness.
Rabbit-Ocular 3.36 - 33.6 mg/kg Minimal conjunctival congestion.
Irritation
(30 days)
Rabbit-Ocular 6.72 mg/day Minimal-moderate conjunctival congestion;
Irritation Minimal-moderate transient conjunctival
(1 year) discharge; isolated instances of minimal flare, iritis, corneal cloudiness and neovascularization.
Rabbit - Ocular 6.72 mg/day Minimal conjunctival congestion:
Irritation transient minimal discharge.
(1 month)
Rat - Enzyme 30,100 No microsomal enzyme-inducing capacity.
Induction mg/kg/day
(14 days)
REFERENCES
- 1. Allen RC. Betaxolol in pulmonary patients. Presented at Southern Medical Assn. Meeting, Baltimore, Maryland, November, 1983.
- 2. Allen RC, Epstein DL. A double-masked clinical trial of betaxolol and timolol in glaucoma patients. ARVO Investigative Ophthalmology and Visual Sciences 22(3): March, 1982.
- 3. Atkins JM, Pugh BR (Jr.), Timewell RM. Cardiovascular effects of topical beta-blockers during exercise. Am J Ophthal 99:173-175 (Feb), 1985.
- 4.
Armstrong JM, Cavero I, Fenard S. The contribution of sympathetic and parasympathetic nerve mechanisms to the control of heart rate in conscious dogs at rest and during exercises as assessed by using betaxolol and methyltropine.
Br J. Pharmacol 73:288-289P, 1981.
- 5. Barrett AM. Therapeutic applications of β-adrenoceptor antagonists. in: Morselli PL, Kilborn JR, et al (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 65-72, 1983.
6 Beresford R, Heel RC: Betaxolol: a review of its pharmacodynamics and pharmacokinetic properties, and therapeutic efficacy in hypertension.
Drugs 31:6-28, 1986.
- 7. Berrospi AR, Leibowitz HM. Betaxolol, a new beta-adrenergic blocking agent for treatment of glaucoma. Arch Ophthal 100:943-946, 1982.
- 8. Berry D. Betaxolol. Presented at Harvard Medical School - Glaucoma Conference, Boston, Mass., June, 1983.
- 9. Berry DP Jr, Van Buskirk EM, Shields MB. Betaxolol and timolol: a comparison of efficacy and side effects. Arch Ophthal 102:42-45, 1984.
- 10. Bessho H, Suzuki J, Tobe A. Vascular effects of betaxolol, a cardioselective β-adrenoceptor antagonist, in isolated rat arteries. Jap J Pharmacol 55:351-358, 1991.
- 11. Boles Carenini A, Sibour G, Boles Carenini B. Differences in the long-term effect of timolol and betaxolol on the pulsatile ocular blood flow. Surv Ophthalmol 38 (Suppl): S118-S124, 1994.
- 12. Boudot JP, Cavero I, et al. Preliminary studies on SL 75212, a new potent cardioselective β -adrenoceptor antagonist. Br J Clin Pharm 7:445, 1979 (abstr.).
- 13.
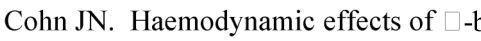 -blockers. Drugs 25 (Suppl 2):100-102, 1983.
- 14. Collignon-Brach J. Long-term effect of topical beta-blockers on intraocular pressure and visual field sensitivity in ocular hypertension and chronic open-angle glaucoma. Surv Ophthalmol 38 (Suppl): S149-S155, 1994.
- 15. Cruickshank JM. How safe are β-blockers? Drugs 25 (Suppl 2):331-340, 1983.
- 16. Fechtner RD, & Weinreb RN. Mechanisms of optic nerve damage in primary open angle glaucoma. Surv Ophthalmol 39:23-42, 1994.
- 17. Flammer J. The vascular concept of glaucoma. Surv Ophthalmol 38: S3 - S6, 1994.
- 18. Ferrandes B, Durand A, et al. Pharmacokinetics and metabolism of betaxolol in various animal species and man. in: Morselli PL, Kilborn JR, et al (eds): Betaxolol and Other β -1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 51-64, 1983.
- 19. Friedmann J-C. Safety evaluation of betaxolol. in: Morselli PL, Kilborn JR, et al (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 43-50, 1983.
- 20. Hernandez HH, Cervantes R, Frati A, et al. Cardiovascular effects of topical glaucoma therapies in normal subjects. J. Toxicol 2 (2-3):99-106, 1983.
- 21. Hester RK, Chen Z, Becker EJ, McLaughlin M, DeSantis L. The direct vascular relaxing action of betaxolol, carteolol and timolol in porcine long posterior ciliary artery. Surv Ophthalmol 38(Suppl):S125-S134, 1994.
- 22. Hoste AM, Sys SU. The relaxant actions of betaxolol on isolated bovine retinal microarteries. Curr Eye Res 5:483-487, 1994.
- 23.
Hoste AM, Boels PJ, Andries LJ, Brutsaert DL, Ke Laey JJ. Effects of beta-antagonists on contraction of bovine retinal arteries in vitro.
Invest Ophthalmol Vis Sci 31:1231-1237, 1990.
- 24. Huckauf H. Respiratory tolerance of oral betaxolol in partially reversible obstructive airways disease. in: Morselli PL, Kilborn JR, et al (eds):Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 205-211, 1983.
- 25. Hugues FC, Julien D, Marche J. Influence of betaxolol HCl and atenolol on airways in chronic obstructive lung diseases: comparison with propranolol. in: Morselli PL. Kilborn JR, et at (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 195-203, 1983.
- 26. Kaiser HJ, Flammer J, Stümpfig D, Hendrickson P. Long-term visual field follow-up of glaucoma patients treated with beta-blockers. Surv Ophthalmol 38 (Suppl): S156-S159, 1994.
- 27. Manoury P. Betaxolol: Chemistry and biological profile in relation to its physico-chemical properties. in: Morselli PL, Kilborn JR, et at (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 13-20, 1983.
- 28. Manoury P, Langer SZ, Galzin AM, et al. Basic Sciences. In: Morselli PL, Kilborn JR, et al, (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 13-72, 1983.
- 29. Osborne NN, Cazvieille C, Carvalho AL, Larson A, DeSantis L. In vivo and in vitro experiments show that betaxolol is a neuroprotective agent. Invest Ophthalmol Vis Sci 37(3, Suppl):S836, 1996. Submitted for publication to Invest Ophthalmol Vis Sci,(1-16), 1996.
- 30. Reiss GR, Brubaker RF. The mechanism of betaxolol, new ocular hypotensive agent. Ophthalmology 90:1369-1372, 1983.
- 31. Robertson JIS. State-of-the-art review: β-blockade and the treatment of hypertension. Drugs 25 (Suppl 2):5-11, 1983.
- 32. Satoh N, Suzuki J, Bessho H, Kitada Y, Narimatsu A, Tobe A. Effects of betaxolol on cardiohemodynamics and coronary circulation in anesthetized dogs: comparison with atenolol and propranolol. Japan J Pharmacol 54:113-119, 1990.
- 33. Schoene RB, Abuan T, Ward RL, Beasley CH. Effects of betaxolol, timolol and placebo on pulmonary function in asthmatic bronchitis. AM J Ophthal 97:86-92, 1984.
- 34. Schoene RB, Abuan T, el al. Topical betaxolol HCl, timolol, and placebo in asthmatic bronchitis: Effects of pulmonary function. Presented at American Academy of Ophthalmology, Chicago, November, 1983.
- 35. Setoguchi M, Ohya Y, Abe I, Fujishima M. Inhibitory action of betaxolol, a β1-selective adrenoceptor antagonist, on voltage-dependent calcium channels in guinea-pig artery and vein. Brit J Pharmacol 115:198-202, 1995.
- 36. Shanks RG et al. Clinical pharmacology. in: Morselli PL, Kilborn JR, et al (eds): Betaxolol and Other β-1Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 73-241, 1983.
- 37. Sonksen PH, Brown PM, et al. Metabolic and cardiovascular effects of betaxolol during hypoglycemia and exercise in normal volunteers. In: Morselli PL, Kilborn JR, et al (eds): Betaxolol and Other β-1-Adrenoceptor Antagonists, Vol 1, L.E.R.S. Monograph Series, New York, Raven Press, pp. 143-154, 1983.
- 38. Yu DY, Su EN, Cringle SJ, Alder VA, Yu PK, DeSantis L. Intra- and extra-luminal betaxolol dilates potassium contracted perfused porcine retinal arteries and branches. Invest Ophthalmol Vis Sci 37(3, Suppl):S844, 1996. Submitted for publication to Invest Ophthalmol Vis Sci,(1-15), 1996.