


Product Monograph - Brimonidine (Micro Labs)
RECENT MAJOR LABEL CHANGES
None at the time of the most recent authorization.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS .................................................................................................... 4
1.1 Pediatrics ..................................................................................................... 4
1.2 Geriatrics ...................................................................................................... 4
2 CONTRAINDICATIONS ....................................................................................... 4
4 DOSAGE AND ADMINISTRATION ....................................................................... 4
4.1 Dosing Considerations ................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ............................................. 4
4.4 Administration ............................................................................................. 5
4.5 Missed Dose ................................................................................................. 5
5 OVERDOSAGE ................................................................................................... 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ....................... 6
7 WARNINGS AND PRECAUTIONS ........................................................................ 6
7.1 Special Populations ...................................................................................... 8
7.1.1 Pregnant Women ......................................................................................... 8
7.1.2 Breast-feeding ............................................................................................. 8
7.1.3 Pediatrics ..................................................................................................... 8
7.1.4 Geriatrics ..................................................................................................... 9
8 ADVERSE REACTIONS ........................................................................................ 9
8.1 Adverse Reaction Overview ......................................................................... 9
8.2 Clinical Trial Adverse Reactions .................................................................... 9
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .............................................. 11
8.3 Less Common Clinical Trial Adverse Reactions ........................................... 11
8.5 Post-Market Adverse Reactions ................................................................. 11
9 DRUG INTERACTIONS ...................................................................................... 12
9.2 Drug Interactions Overview ....................................................................... 12
9.3 Drug-Behavioural Interactions ................................................................... 12
9.4 Drug-Drug Interactions .............................................................................. 12
9.5 Drug-Food Interactions .............................................................................. 12
9.6 Drug-Herb Interactions .............................................................................. 12
9.7 Drug-Laboratory Test Interactions ............................................................. 13
10 CLINICAL PHARMACOLOGY ............................................................................. 13
10.1 Mechanism of Action ................................................................................. 13
10.2 Pharmacodynamics .................................................................................... 14
10.3 Pharmacokinetics ....................................................................................... 15
11 STORAGE, STABILITY AND DISPOSAL ............................................................... 16
12 SPECIAL HANDLING INSTRUCTIONS ................................................................. 16
PART II: SCIENTIFIC INFORMATION ........................................................................................ 17
13 PHARMACEUTICAL INFORMATION .................................................................. 17
14 CLINICAL TRIALS .............................................................................................. 18
14.1 Clinical Trial by Indication .......................................................................... 18
15 MICROBIOLOGY .............................................................................................. 20
16 NON-CLINICAL TOXICOLOGY ........................................................................... 20
17 SUPPORTING PRODUCT MONOGRAPHS .......................................................... 23
PATIENT MEDICATION INFORMATION ................................................................................... 24
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
BRIMONIDINE (brimonidine tartrate) is indicated for:
- the control of intraocular pressure in patients with chronic open-angle glaucoma or ocular hypertension
1.1 Pediatrics
Pediatrics (< 18 years of age): The safety and efficacy of brimonidine tartrate has not been established in pediatric patients; therefore, Health Canada has not authorized an indication for pediatric use. Several serious adverse reactions have been reported in association with the administration of brimonidine tartrate ophthalmic solution 0.2% in pediatric populations. See 2 CONTRAINDICATIONS, 7.1.3 Pediatrics and 8.2.1 Clinical Trial Adverse Reactions – Pediatrics.
1.2 Geriatrics
Geriatrics (> 65 years of age): No overall difference in safety and effectiveness has been observed between elderly and other adult patients.
2 CONTRAINDICATIONS
BRIMONIDINE is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or components of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients receiving monoamine oxidase (MAO) inhibitor therapy.
- Neonates and infants (children under the age of 2 years).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Patients should be advised that if they have ocular surgery or develop any type of ocular condition, they should immediately seek their doctor's advice concerning the continued use of the present bottle.
4.2 Recommended Dose and Dosage Adjustment
- The recommended dose is one drop of BRIMONIDINE in the affected eye(s) twice daily (BID) (doses taken approximately 12 hours apart).
Health Canada has not authorized an indication for pediatric use.
4.4 Administration
Do not allow the dropper tip of the bottle to touch the eye or other surrounding structures, because this could cause eye injury or contaminate the tip with common bacteria known to cause eye infections. Serious damage to the eye and subsequent loss of vision may result from using contaminated solutions.
Patients Wearing Soft Contact Lenses:
Lenses should be removed prior to the application of BRIMONIDINE and not re-inserted earlier than 15 minutes after administration.
4.5 Missed Dose
A missed dose should be applied as soon as the patient remembers. The regular dosing schedule should then be resumed with the next dose. Patients should not apply more than one dose at a time in an effort to catch up on missed doses.
5 OVERDOSAGE
In ophthalmic overdose cases that have been received, the events reported have generally been those already listed as adverse reactions.
Systemic overdose resulting from accidental ingestion:
There is very limited information regarding accidental ingestion of brimonidine in adults. The only adverse event reported to date was hypotension. Treatment of an oral overdose includes supportive and symptomatic therapy; a patient’s airway should be maintained. Evacuation of the stomach should be considered during the first few hours after an overdosage.
Symptoms of brimonidine overdose such as apnea, bradycardia, coma, hypotension, hypothermia, hypotonia, lethargy, pallor, respiratory depression, and somnolence have been reported in neonates, infants, and children receiving brimonidine tartrate as part of medical treatment of congenital glaucoma or by accidental oral ingestion. See 2 CONTRAINDICATIONS.
| For management of a suspected drug overdose, including accidental ingestion, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Ophthalmic | Solution, 0.2% w/v | Contains 0.005% w/v benzalkonium chloride as preservative, citric acid, polyvinyl alcohol, water for injection, sodium chloride and sodium citrate. Hydrochloric acid and/or sodium hydroxide may be added to adjust pH. The pH range of BRIMONIDINE solution is 5.9 to 6.5. |
BRIMONIDINE is a sterile, clear, greenish yellow color solution, free from any visible particles, supplied in 5 mL, 10 mL and 15 mL bottles as follows:
| Unit Count or Fill Size | Container Size(s) | Description |
| 5 mL | 5 mL in 10 mL, 3-piece LDPE S-design container | 5 mL fill in 10 mL 3-piece LDPE S-design container with white LDPE S open Nozzle and Purple color HDPE S cap with TSTR-Tear off Ring cap in a Carton along with leaflet. |
| 10 mL | 10 mL in 10 mL, 3-piece LDPE S-design container | 10 mL fill in 10 mL 3-piece LDPE S-design container with white LDPE S open Nozzle and Purple color HDPE S cap with TSTR-Tear off Ring in a Carton along with leaflet. |
| 15 mL | 15 mL in 15 mL, 3-piece LDPE S-design container | 15 mL fill in 15 mL 3-piece LDPE S-design container with white LDPE S open Nozzle and Purple Color HDPE S cap with TSTR-Tear off Ring. |
7 WARNINGS AND PRECAUTIONS
General
FOR TOPICAL OPHTHALMIC USE ONLY.
Carcinogenesis and Mutagenesis
No compound-related carcinogenic effects were observed in 21 month and 2 year studies in mice and rats given oral doses of 2.5 mg base/kg/day and 1.0 mg base/kg/day of brimonidine tartrate, respectively. These oral doses are approximately 830 and 330 times greater, respectively, than the maximum recommended human daily ophthalmic dosage for brimonidine tartrate (0.003 mg base/kg/day), based on a 60 kg human.
Brimonidine was not mutagenic or cytogenic in a series of in vitro and in vivo studies including the Ames test, host-mediated assay, chromosomal aberration assay in Chinese Hamster Ovary (CHO) cells, cytogenic studies in mice and the dominant lethal assay.
Cardiovascular
Although brimonidine tartrate had minimal effect on blood pressure and heart rate of patients in clinical studies, caution should be exercised in treating patients with severe cardiovascular disease.
BRIMONIDINE should be used with caution in patients with cerebral or coronary insufficiency, Raynaud's phenomenon, orthostatic hypotension or thromboangiitis obliterans.
Driving and Operating Machinery
BRIMONIDINE, as with other similar medications, can potentially cause fatigue and/or drowsiness in some patients. Patients who engage in hazardous activities should be cautioned of the potential for a decrease in mental alertness.
BRIMONIDINE may also cause blurred vision or visual disturbance in some patients. The patient should wait until these symptoms have cleared before driving or using machinery.
Hepatic/Biliary/Pancreatic
Brimonidine tartrate has not been studied in patients with hepatic impairment; caution should be exercised in treating such patients.
Ophthalmologic
The preservative in BRIMONIDINE, benzalkonium chloride, may be absorbed by soft contact lenses. Patients wearing soft contact lenses should be instructed to wait at least 15 minutes after instilling BRIMONIDINE to insert soft contact lenses.
Delayed ocular hypersensitivity reactions have been reported with brimonidine tartrate ophthalmic solution, with some reported to be associated with an increase in intraocular pressure (IOP). See 8 ADVERSE REACTIONS.
Psychiatric
BRIMONIDINE should be used with caution in patients with depression.
Renal
Brimonidine tartrate has not been studied in patients with renal impairment; caution should be exercised in treating such patients.
Sensitivity/Resistance
BRIMONIDINE should be used with caution in patients with known hypersensitivity to other alpha-adrenoceptor agonists.
7.1 Special Populations
7.1.1 Pregnant Women
Teratogenicity studies showed no adverse effects in rats and rabbits when oral doses (1.65 mg base/kg/day and 3.33 mg base/kg/day of brimonidine tartrate, respectively) were administered at approximately 550 and 1110 times, respectively, the maximum recommended human daily ophthalmic dosage for brimonidine tartrate based on a 60 kg human.
There are no studies of brimonidine tartrate in pregnant women; however, in animal studies, brimonidine crossed the placenta and entered into the fetal circulation to a limited extent (ratio of drug-related material in fetal:maternal blood = 0.1 - 0.3). Drug-derived material was eliminated from fetal tissues by 24 hours post-dose. BRIMONIDINE should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus.
7.1.2 Breast-feeding
It is not known whether brimonidine is excreted in human milk; however, in animal studies, brimonidine has been shown to be excreted in breast milk. During treatment with BRIMONIDINE, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Neonates and infants (children under the age of 2 years): The use of BRIMONIDINE in neonates and infants is contraindicated. Several serious adverse reactions have been reported in association with the administration of brimonidine tartrate ophthalmic solution 0.2% to infants in the age range of 28 days to 3 months. See 2 CONTRAINDICATIONS and 8.2.1 Clinical Trial Adverse Reactions – Pediatrics.
Children (2-18 years of age): The use of BRIMONIDINE is currently not recommended in children, as several serious adverse reactions have been reported in association with the administration of brimonidine tartrate ophthalmic solution 0.2% in the pediatric population. See 8.2.1 Clinical Trial Adverse Reactions – Pediatrics.
7.1.4 Geriatrics
No overall difference in safety and effectiveness has been observed between elderly and other adult patients. The Cmax and apparent half-life of brimonidine tartrate were similar in elderly subjects (65 years or older) and younger adults, indicating that its systemic absorption and elimination were not significantly affected by age.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Two 12-month Phase 3 clinical studies and 3 ancillary clinical studies were conducted with brimonidine tartrate. Based on the clinical data, the most commonly reported adverse drug reactions were oral dryness (25.8%), ocular hyperemia (24.8%), burning and stinging (22.5%), blurring (17.3%), headache (16.3%), foreign body sensation (15.5%), fatigue/drowsiness (15.2%). Ocular allergic reactions (including allergic blepharoconjunctivitis, allergic conjunctivitis, follicular conjunctivitis) were the most frequent cause for discontinuation in the clinical trials (8.5%). Oral dryness and ocular hyperemia, although frequently reported, were infrequent causes for discontinuation at 1.1% and < 1%, respectively. Serious adverse events (AEs) were reported for a total of 23 patients (3.0%); none of the serious AEs were ocular and none were considered treatment related.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Table 2 – Treatment-Related Adverse Reactions Occurring at ≥ 1% with Brimonidine Tartrate
Brimonidine 0.2% n = 717 (%) | Timolol 0.5% n = 413 (%) | |
|---|---|---|
| Eye disorders | ||
| ocular hyperemia | 178 (24.8%) | 104 (25.2%) |
| burning and stinging | 161 (22.5%) | 180 (43.6%) |
| blurring | 124 (17.3%) | 93 (22.5%) |
| foreign body sensation | 111 (15.5%) | 69 (16.7%) |
| corneal staining/erosion | 72 (10.0%) | 48 (11.6%) |
| ocular allergic reactionsa | 71 (9.9%) | 1 (0.2%) |
| ocular pruritus | 70 (9.8%) | 42 (10.2%) |
| conjunctival follicles | 69 (9.6%) | 23 (5.6%) |
| photophobia | 53 (7.4%) | 42 (10.2%) |
| ocular dryness | 50 (7.0%) | 40 (9.7%) |
| eyelid erythema | 44 (6.1%) | 22 (5.3%) |
| ocular ache/pain | 43 (6.0%) | 18 (4.4%) |
| lacrimation disorder | 40 (5.6%) | 21 (5.1%) |
| conjunctival edema | 38 (5.3%) | 26 (6.3%) |
| eyelid edema | 35 (4.9%) | 13 (3.1%) |
| conjunctival blanching | 27 (3.8%) | 16 (3.9%) |
| blepharitis | 26 (3.6%) | 12 (2.9%) |
| ocular irritation | 22 (3.1%) | 6 (1.5%) |
| abnormal vision | 19 (2.6%) | 15 (3.6%) |
| conjunctival discharge | 10 (1.4%) | 7 (1.7%) |
| conjunctival papillae | 7 (1.0%) | 9 (2.2%) |
| Gastrointestinal | ||
| oral dryness | 185 (25.8%) | 69 (16.7%) |
| gastrointestinal symptoms | 22 (3.1%) | 14 (3.4%) |
| abnormal taste | 10 (1.4%) | 5 (1.2%) |
| General disorders and administration site conditions | ||
| fatigue/drowsiness | 109 (15.2%) | 62 (15.0%) |
| systemic other | 32 (4.5%) | 25 (6.1%) |
| asthenia | 20 (2.8%) | 7 (1.7%) |
| Nervous system disorders | ||
| headache | 117 (16.3%) | 83 (20.1%) |
| dizziness | 30 (4.2%) | 15 (3.6%) |
| Respiratory, thoracic and mediastinal disorders | ||
| upper respiratory symptoms | 43 (6.0%) | 21 (5.1%) |
| nasal dryness | 7 (1.0%) | 4 (1.0%) |
a It should be noted that ocular allergic reaction includes allergic blepharitis, allergic blepharoconjunctivits, allergic conjunctivitis, allergic reaction (ocular) and follicular conjunctivitis.
Based on safety data from two pivotal clinical studies and three ancillary studies conducted on brimonidine tartrate, most adverse reactions were transient and not commonly of a severity requiring discontinuation of treatment. Adverse events were coded using the COSTART dictionary available at the time of the study but are presented in Table 2 above using MedDRA System Organ Class.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In a 3-month, phase 3 study in children aged 2-7 years with glaucoma, inadequately controlled by beta-blockers, a high prevalence of somnolence (55%) was reported with brimonidine tartrate as adjunctive treatment. In 8% of children, this was severe and led to discontinuation of treatment in 13%. The incidence of somnolence decreased with increasing age, being least in the 7-year-old age group (25%), but was more affected by weight, occurring more frequently in those children weighing ≤ 20 kg (63%) compared to those weighing > 20 kg (25%).
The safety and effectiveness of brimonidine tartrate ophthalmic solution has not been studied in children under the age of two years. During post-marketing surveillance, somnolence, lethargy, hypotonia, hypothermia, bradycardia, hypotension, apnoea, respiratory depression, pallor and coma have been reported in neonates, infants and children receiving brimonidine either for congenital glaucoma or via accidental ingestion. See 2 CONTRAINDICATIONS and 7.1.3 Pediatrics.
8.3 Less Common Clinical Trial Adverse Reactions
Cardiac disorders: palpitations
Immune system disorders: systemic allergic reactions
Psychiatric disorders: depression
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-marketing use of brimonidine tartrate ophthalmic solution, 0.2% w/v in clinical practice. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
Cardiac disorders: palpitations/arrhythmias (including bradycardia or tachycardia)
Eye disorders: iritis, iridocyclitis (anterior uveitis), miosis, conjunctivitis, eyelids pruritus
Immune system disorders: hypersensitivity
Nervous system disorders: syncope
Psychiatric disorders: depression
Skin and subcutaneous tissue disorders: skin reaction
Vascular disorders: hypotension
The following adverse reactions have been identified during post-marketing use of brimonidine tartrate ophthalmic solution, 0.15% w/v in clinical practice. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made.
Eye disorders: vision blurred, conjunctivitis
General disorders and administration site conditions: fatigue
Immune system disorders: hypersensitivity
Nervous system disorders: dizziness, somnolence
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Brimonidine tartrate did not have clinically significant effects on pulse and blood pressure in chronic clinical studies. However, since alpha-agonists, as a class, may reduce pulse and blood pressure, caution in the concomitant use of drugs such as beta-blockers (ophthalmic and/or systemic), antihypertensives, and/or cardiac glycosides is advised.
9.3 Drug-Behavioural Interactions
No formal drug-behavioural interaction studies were conducted with brimonidine tartrate .
9.4 Drug-Drug Interactions
Tricyclic antidepressants have been reported to blunt the hypotensive effect of systemic clonidine. It is not known whether the concurrent use of these agents with brimonidine tartrate can lead to an interference in IOP lowering effect. No data are available on the level of circulating catecholamines after brimonidine tartrate is instilled. Caution, however, is advised in patients taking tricyclic antidepressants which can affect the metabolism and uptake of circulating amines.
Although specific drug interaction studies have not been conducted with brimonidine tartrate, the possibility of an additive or potentiating effect with central nervous system (CNS) depressants (e.g., alcohol, barbiturates, opiates, sedatives, or anesthetics) should be considered.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Brimonidine tartrate is a relatively selective alpha-2-adrenergic receptor agonist that in radioligand binding assays and in functional assays, is approximately 1000 times more selective for the alpha-2 adrenoceptor than the alpha-1 adrenoceptor. This selectivity results in the absence of vasoconstriction in microvessels associated with human retinal xenografts.
Topical administration of brimonidine decreases IOP in humans. When used as directed, brimonidine tartrate reduces elevated IOP with minimal effect on cardiovascular parameters.
Brimonidine tartrate has a rapid onset of action, with the peak ocular hypotensive effect occurring at approximately two hours post-dosing. The duration of effect is 12 hours or greater.
Fluorophotometric studies in animals and humans suggest that brimonidine tartrate has a dual mechanism of action. Brimonidine tartrate lowers IOP by reducing aqueous humor production and increasing uveoscleral outflow.
The effect of brimonidine on aqueous humour dynamics was determined in 21 ocular hypertensive patients. Measurements were made at baseline and following one week (Day 8) of BID application of one drop of brimonidine tartrate 0.2% to one eye and vehicle to the other eye, in a double-blind fashion. The results of this study (mean ± SEM) are reported in Table 3. They indicate that brimonidine reduces IOP in humans by decreasing aqueous inflow and increasing uveoscleral outflow.
Table 3 – Effects of Brimonidine on Aqueous Humour Dynamics
| Control Eye | Treated Eye | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Baseline | Day 8 | Baseline | Day 8 | |||||||||||
| IOP | 21.3 ± 1.0 | 20.0 ± 0.6* | 20.6 ± 0.8 | 15.9 ± 0.6*† | ||||||||||
| Fa | 2.6 ± 0.2 | 2.3 ± 0.1* | 2.5 ± 0.2 | 2.0 ± 0.1* | ||||||||||
| Fufl | 0.35 ± 0.20 | 0.50 ± 0.17 | 0.12 ± 0.28 | 0.65 ± 0.16* | ||||||||||
| Futon | 0.28 ± 0.31 | 0.08 ± 0.35 | 0.25 ± 0.37 | 1.02 ± 0.11*† | ||||||||||
| Cfl | 0.22 ± 0.03 | 0.16 ± 0.02* | 0.22 ± 0.03 | 0.21 ± 0.03 | ||||||||||
| Cton | 0.17 ± 0.01 | 0.19 ± 0.02 | 0.19 ± 0.03 | 0.16 ± 0.02 | ||||||||||
| Pev | 8.9 ± 0.5 | 8.5 ± 04 | 8.8 ± 0.5 | 9.2 ± 0.3 | ||||||||||
*p≤0.05 vs baseline
†p≤0.05 vs control
Fa = aqueous flow (mcL/min)
Cfl = outflow capacity (mcL/min/mmHg)
IOP = intraocular pressure (mmHg)
Cton = tonographic outflow facility (mcL/min/mmHg)
Pev = episcleral venous pressure (mmHg)
Fufl = uveoscleral outflow by fluorophotometry (mcL/min)
Futon = uveoscleral outflow by tonography (mcL/min)
10.2 Pharmacodynamics
Brimonidine tartrate has no effect on pulmonary function or exercise-induced tachycardia. The cardiovascular effects of brimonidine tartrate during exercise in normal volunteers were found to be limited to a slight suppression of systolic blood pressure, which was clinically insignificant, during the recovery period following a treadmill test.
In short-term studies (up to four days) in normal healthy volunteers, brimonidine tartrate ophthalmic solution preserved with benzalkonium chloride lowered IOP significantly better than vehicle at all concentrations tested (0.02 - 0.5%) and was found to be safe and comfortable. At these concentrations, the peak effect on IOP was observed between one and four hours post-instillation. The greatest reduction in IOP was dose-related, reaching a maximal decrease from baseline of up to 40% with brimonidine tartrate 0.5%. In the morning (12 hours after the evening instillation), the 0.08% and 0.2% concentrations reached a maximal IOP lowering effect following two days of BID dosing. This was observed with the 0.5% concentration, 12 hours after the first instillation. Conjunctival blanching was observed primarily at the 0.35% and 0.5% concentrations and was generally mild or moderate in nature. There was a significantly greater incidence of dry eye seen only with brimonidine tartrate 0.5% as compared to vehicle, although this finding was also reported at the lower concentrations. The overall mean decrease in pupil size and systolic blood pressure was generally greater with brimonidine 0.2% and 0.5% than with vehicle. This change in systolic blood pressure was not judged to be clinically significant. Heart rate, diastolic blood pressure, visual acuity and cup-disc ratio did not appear to be significantly affected by brimonidine treatment (as compared to vehicle). Additionally, at the concentrations tested in these healthy volunteer studies, a contralateral effect of brimonidine was not observed.
When evaluated in open-angle glaucoma and ocular hypertensive patients at concentrations of 0.08%, 0.2% and 0.5% for one month (BID), brimonidine tartrate was found to be both efficacious and safe. All concentrations tested were significantly more effective than vehicle in lowering elevated IOP. The two higher concentrations of brimonidine tartrate were also more effective than the 0.08% concentration. Brimonidine tartrate 0.5%, however, was not any more effective than 0.2% for long-term treatment. The peak effect on IOP occurred at two hours for brimonidine tartrate 0.08%, 0.2%, and 0.5%. The greatest decrease in IOP was dose-related, with a maximum reduction of 27% from baseline with brimonidine tartrate 0.2%, and 31% from baseline with brimonidine tartrate 0.5%. Brimonidine tartrate 0.5% was associated with a greater incidence of side effects than brimonidine tartrate 0.2% and 0.08%, including blurring, foreign body sensation, fatigue and drowsiness. Dry mouth was seen more often in all active treatment groups than in the vehicle group. This event was also seen at a higher incidence with brimonidine tartrate 0.5% than with brimonidine tartrate 0.08%. Although heart rate did not appear to be significantly affected by brimonidine treatment, diurnal measurements of blood pressure indicated that brimonidine tartrate 0.5% was associated with a greater decrease than was vehicle or the lower brimonidine strengths. The mean blood pressure decreases observed were not considered to be clinically significant.
10.3 Pharmacokinetics
Table 4 – Summary of Brimonidine Pharmacokinetic Parameters in Healthy Volunteers
Cmax (ng/mL) | Tmax (hr) | t½ (hr) | AUC0-12hr | |
|---|---|---|---|---|
BID for 10 days mean | 0.0585 | 1-4 | 3 | 0.309 |
Absorption
After ocular administration of brimonidine tartrate BID (both eyes) in humans for 10 days, plasma concentrations were low (mean Cmax=0.06 ng/mL). With both brimonidine tartrate concentrations, plasma brimonidine levels peaked within 1 to 4 hours and declined with a systemic half-life of approximately 3 hours.
Systemic absorption of brimonidine after ocular administration of a single dose (both eyes) of brimonidine tartrate 0.08%, 0.2% and 0.5% to healthy volunteers, produced dose-dependent increases in Cmax and AUC. AUC increased proportionally with dose between the 0.08% and 0.2% doses; the increase in AUC of the 0.5% dose was less than proportional with the increase in dose. Following the 0.5% dose, plasma Cmax and AUC0-4 were approximately 0.1 ng/mL and 0.5 ng·hr/mL, respectively. The mean Tmax was 2 - 3 hours for all concentrations tested in this study. In general, plasma concentrations declined to undetectable levels by 12 hours post-dose. The apparent plasma t1/2 ranged from 2 to 5 hours (mean = 3.3 hours).
Metabolism
Brimonidine is metabolized primarily by the liver.
Elimination
In humans, brimonidine is eliminated rapidly via extensive systemic metabolism. There is no marked systemic accumulation after multiple dosing. Urinary excretion is the major route of elimination of the drug and its metabolites. Approximately 87% of an orally-administered radioactive dose was eliminated within 120 hours, with 74% found in the urine.
Special Populations and Conditions
Geriatrics: Plasma concentration-time profiles were similar for both young and elderly healthy volunteers following ocular instillation of a single dose of brimonidine tartrate
- 0.2%, although the elderly subjects showed a tendency to have a slightly greater systemic exposure to brimonidine. Steady state concentrations were reached by day 7 of multiple dosing (both eyes, BID) in young (23 - 39 years) subjects. Twice daily ocular dosing for 10 days did not change the systemic absorption and disposition parameters of brimonidine in young subjects. The mean Cmax was 0.0585 ng/mL and mean AUC0-12 was 0.309 ng·hr/mL after multiple dosing. There was a slight systemic drug accumulation after repeated dosing (accumulation factor: 1.4), consistent with an apparent half-life of 3 hours. Beyond 12 hours after the final dose, plasma concentrations were undetectable or approached the limit of quantitation. Systolic and diastolic blood pressures were generally lowered by brimonidine tartrate administration. These decreases in blood pressure tended to be slightly greater among the elderly subjects than among the young subjects.
11 STORAGE, STABILITY AND DISPOSAL
BRIMONIDINE should be stored at 15 to 25°C. Protect from light. Discard unused portion 28 days after opening.
Keep out of sight and reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
Patients should be advised to avoid touching the tip of the bottle to the eye or any surface, as this may contaminate the solution. Refer to 4.4 Administration for more detailed information.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Brimonidine tartrate |
|---|---|
| Chemical name: | 5-Bromo-6-(2-imidazolidinylideneamino) quinoxaline L-tartrate |
| Molecular formula and molecular mass: | C11H10BrN5 · C4H6O6 and 442.24 g/mol |
| Structural formula: | 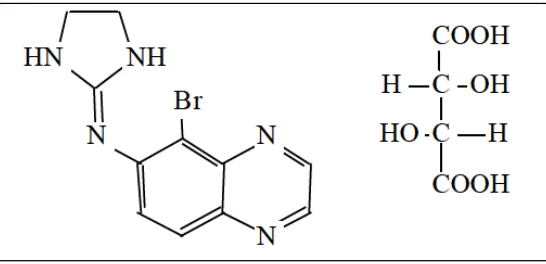 |
| Physicochemical properties: | Brimonidine tartrate is a white or slightly yellowish or slightly brownish powder, with a melting point range of 209.64°C - 211.95°C. It is soluble in water, practically insoluble in ethanol, methanol, toluene and ethyl acetate. The pH of a 1% solution of brimonidine tartrate in water is 3.54 to 3.55 at room temperature. A pKa value of 4.27 has been determined by potentiometric titration. |
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
Control of Intraocular Pressure
Table 5 – Summary of patient demographics for clinical trials in the control of intraocular pressure
| Stud y # | Study design | Dosage, route of administratio n and duration | Study subjects (n) | Mean age (Range ) | Sex | |||||
|---|---|---|---|---|---|---|---|---|---|---|
| No. Entere d | No. Complete d | No. in Preferre d Analysis | ||||||||
| 103-7831 | Multicentre, randomized , double-blind, parallel, active control | One drop in each eye twice daily B - Brimonidine 0.2% T - Timolol 0.5% 1 year | 443 B – 221 T – 222 | 286 B – 119 T – 167 | 394 B – 186 T – 188 | 62.5 (28-84) B – 62.7 (28-84) T – 62.2 (34-83) | 107/12 5 B – 84/102 T – 103/85 | |||
| 104-7831 | Multicentre, randomized , double-blind, parallel, active control | One drop in each eye twice daily B - Brimonidine 0.2% T - Timolol 0.5% 1 year | 483 B – 292 T – 191 | 305 B – 156 T – 149 | 463 B – 280 T – 183 | 62.3 (28-86) B – 63.0 (28-86) T – 61.4 (33-83) | 234/22 9 B – 138/14 2 T – 96/87 | |||
* uneven randomization – 3:2 ratio, brimonidine
Table 6 – Results of studies 103-7831 and 104-7831 in the control of intraocular pressure – intraocular pressure values (mm Hg) phase 3 studies (preferred analysis)
| Study 103-7831 | Study 104-7831 | ||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Brimonidine Tartrate (0.2%) n = 186 | TIMOLOL (0.5%) n = 188 | Brimonidine Tartrate (0.2%) n = 274 | TIMOLOL (0.5%) n = 180 | ||||||||||||||
| Baselin e | Hour-0 | ||||||||||||||||
| Mean | 25.80 | 25.87 | 25.96 | 25.85 | |||||||||||||
| SD | 2.31 | 2.81 | 3.01 | 2.80 | |||||||||||||
| Min / Max | 23.0 / 32.0 | 23.0 / 34.0 | 22.5 / 34.5 | 23.0 / 34.0 | |||||||||||||
| Hour-2 | |||||||||||||||||
| Mean | 24.20 | 24.19 | 25.06 | 24.73 | |||||||||||||
| SD | 3.45 | 3.35 | 3.38 | 3.12 | |||||||||||||
| Min / Max | 15.0 / 34.5 | 12.5 / 34.0 | 17.5 / 36.0 | -19.5 / 2.0 | |||||||||||||
| Month-12 | Hour-0 | ||||||||||||||||
| Mean change from baseline | -3.67 | -5.88 | -3.80 | -5.72 | |||||||||||||
| SD | 3.98 | 3.38 | 3.73 | 3.34 | |||||||||||||
| Min / Max | -11.5 / 8.5 | -16.0 / 6.5 | -12.5 / 6.5 | -13.0 / 5.5 | |||||||||||||
| P-valuea | <0.001 | <0.001 | <0.001 | <0.001 | |||||||||||||
| Hour-2 | |||||||||||||||||
| Mean change from baseline | -5.30 | -5.61 | -7.00 | -5.49 | |||||||||||||
| SD | 3.79 | 3.62 | 4.18 | 3.70 | |||||||||||||
| Min / Max | -13.5 / 8.0 | -14.0 / 4.5 | -20.5 / 2.5 | -12.5 / 6.0 | |||||||||||||
| P-valuea | <0.001 | <0.001 | <0.001 | <0.001 | |||||||||||||
| Overallb | -4.32 | -6.33 | -6.81 | -5.91 | |||||||||||||
n = number of patients at baseline; SD = standard deviation
a = within-group analysis of changes from baseline using paired t-test
b = Least-squares means for IOP changes over the 12 months of study
Brimonidine tartrate lowers IOP with minimal effect on cardiovascular parameters (heart rate, systolic and diastolic blood pressure) and no apparent effect on pulmonary parameters (spirometry, respiratory rate).
The long term efficacy of brimonidine tartrate dosed BID was demonstrated in two one-year multicentre studies in subjects with open angle glaucoma or ocular hypertension. In these trials, brimonidine tartrate lowered IOP by mean values of 4.3 mm Hg at trough and 6.7 mm Hg at peak. IOP decreases were maintained for the duration of the studies in the majority of patients; no tachyphylaxis was observed. Nine percent of subjects were discontinued from the studies due to inadequately controlled IOP.
Plasma concentration-time profiles were similar for both young and elderly healthy volunteers following ocular instillation of a single dose of brimonidine tartrate 0.2%, although the elderly subjects showed a tendency to have a slightly greater systemic exposure to brimonidine. Steady state concentrations were reached by day 7 of multiple dosing (both eyes, BID) in young (23 - 39 years) subjects. Twice daily ocular dosing for 10 days did not change the systemic absorption and disposition parameters of brimonidine in young subjects. The mean Cmax was 0.0585 ng/mL and mean AUC0-12 was 0.309 ng·hr/mL after multiple dosing. There was a slight systemic drug accumulation after repeated dosing (accumulation factor: 1.4), consistent with an apparent half-life of 3 hours. Beyond 12 hours after the final dose, plasma concentrations were undetectable or approached the limit of quantitation. Systolic and diastolic blood pressures were generally lowered by brimonidine tartrate administration. These decreases in blood pressure tended to be slightly greater among the elderly subjects than among the young subjects.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
The acute median lethal dose (LD50) or minimum lethal dose (MLD) values of brimonidine were evaluated in mice, rats, rabbits, and dogs by oral and intravenous (i.v.) administration. The LD50 or MLD values for each study are listed below:
| Species | Route | LD50 (mg/kg)* | MLD (mg/kg)* |
|---|---|---|---|
| Mouse | oral i.v.* | 50 50 | >8** Not performed |
| Rat | oral i.v. | 100 100-150 | >8** Not performed |
| Rabbit | oral i.v. | Not performed Not performed | >6 20-50 |
| Dog | oral i.v. | Not performed Not performed | 0.5 0.05 |
* The doses are expressed as the base except in the mouse and rat MLD data, where they are expressed as brimonidine tartrate.
** The data from additional single dose oral studies of 0.2% and 0.5% solutions of brimonidine tartrate in mice and rats showed that the oral MLD is greater than 10 mg/kg.
The most frequently observed clinical signs in the acute/single dose toxicity studies were primarily due to the exaggerated pharmacological hypotensive effect of the compound. These signs included: sedation, ataxia, prostration, ptosis, reduced/loss of blink reflex, opacification of the cornea, hypotension, bradycardia, hypothermia, respiratory depression, respiratory arrest and circulatory collapse. The ocular changes were seen only after doses at or above the MLD.
Long-term Toxicity
Long-term toxicity studies with brimonidine tartrate in various concentrations using mice, rats, rabbits, dogs and monkeys were conducted for durations of up to one year. The most notable effects seen in these studies were related to the known pharmacological effect of brimonidine.
Brimonidine was administered in repeated oral doses to mice (3 studies – 12 to 13 weeks), rats (6 studies – 6 days to 1 year), dogs (2 studies – 4 to 14 weeks) and monkeys (2 studies – 1 year each). It was also administered ocularly to rabbits (2 studies – 1 and 6 months), dogs (1 study - 4 weeks) and monkeys (1 study - 1 year). There were no observable adverse effects in oral dosing of mice at approximately 165 times the recommended ocular human dose, rats at approximately 80 times the recommended ocular human dose, rabbits at approximately 25 times the recommended ocular human dose, dogs at approximately 55 times the recommended ocular human dose, and monkeys at 33 times the recommended ocular human dose. Dosage levels of approximately 330 times greater than those recommended for human ocular use showed toxic effects that were consistent with the pharmacological class of the compound.
Chronic oral dosing studies were performed at extreme levels of approximately 3000 times the recommended human ocular dose. At these extreme doses, mice showed goblet cell hyperplasia and depletion in the rectum and colon, hypertrophy of the tunica muscularis of small and large intestine, and hyperplasia of the non-glandular epithelium of the stomach. Rats dosed orally at approximately 1500 times the human ocular dose, showed thickening of muscularis mucosa of small intestine, and a dose related incidence of illeal intussusception was observed in all rats, but no associated lesions or morphological changes were observed. Evidence of toxicity characterised by decreased body weight gain and/or decreased food consumption was often seen at the higher oral doses in the mouse, rat and monkey. The most notable effects seen in the subacute studies was an exaggerated pharmacological effect characterised by sedation, ataxia, hypoactivity, ptosis, decreased muscle tone, hypotension and bradycardia.
There were no observable adverse effects in ocular dosing of rabbits up to approximately 120 times the recommended ocular human dose, dogs up to approximately 20 times the recommended ocular human dose, and monkeys up to approximately 40 times the recommended ocular human dose.
Carcinogenicity: There was no compound-related oncogenic effect observed in either mice or rats studies.
The maximal brimonidine plasma concentrations after oral administration of 2.5 mg base/kg/day to mice for 21 months correspond to approximately 77 times the human systemic exposure to brimonidine tartrate 0.2% instilled in each eye (one drop) BID for 10 days, and approximately 44 times the human systemic exposure to brimonidine tartrate 0.5% administered as a single dose (one drop in each eye). After two years of oral administration at 1.0 mg base/kg/day to rats, plasma concentrations were approximately 118 times greater than those seen in humans receiving one drop of brimonidine tartrate 0.2% in each eye BID for 10 days, and approximately 67 times greater than those seen in humans receiving a single dose of brimonidine tartrate 0.5% (one drop in each eye). There were no observable tumorigenic effects seen in mice or rats dosed at 2.5 mg base/kg/day (approximately 830 times the recommended human ocular dose), for up to 24 months.
Genotoxicity: Brimonidine was not mutagenic or cytogenic in a series of in vitro and in vivo studies including the Ames test, host-mediated assay, chromosomal aberration assay in CHO cells, cytogenic studies in mice and the dominant lethal assay.
Reproductive and Developmental Toxicology: Reproductive toxicology studies conducted with brimonidine in rats and rabbits showed that brimonidine had no adverse effects on fertility and general reproductive performance and showed no evidence of embryolethal or teratogenic activity at the dosages administered.
The mean maximal plasma brimonidine concentrations measured during the rat teratogenicity study (1.65 mg base/kg/day, orally) were approximately 333 times the human systemic exposure to brimonidine tartrate 0.2% instilled in each eye (one drop) BID for 10 days, and approximately 189 times the human systemic exposure to brimonidine tartrate 0.5% administered as a single dose (one drop in each eye). Mean maximal plasma brimonidine concentrations in the rabbit teratogenicity study (3.33 mg base/kg/day, orally) were approximately 24 times greater than plasma concentrations seen in humans receiving one drop of brimonidine tartrate 0.2% in each eye BID for 10 days, and approximately 14 times greater than plasma levels seen in humans receiving a single dose of brimonidine tartrate 0.5% (one drop in each eye).
There were no treatment-related reproductive and teratological effects observed in the F1 rat pup group, although a reduction in body weight was observed at a dose level of 1.65 mg base/kg/day, after 14 days. Dose related reduction in body weight gains were observed in rat dams at dose levels of 0.66 and 1.65 mg base/kg/day after 15 days.
In one rabbit study, body weight gain and food consumption in the low and mid-dose groups was comparable to the control group throughout the study. Spontaneous abortions occurred in two of eight rabbits at the 3.3 mg base/kg/day level (gestation day 21 or 23), and may have been the result of the exaggerated pharmacological effects observed at this level. No abortions occurred at the 0.165 or 0.66 mg base/kg/day level. Maternal necropsy was generally unremarkable. There was no evidence of treatment-related embryotoxicity, fetal toxicity, or teratogenicity at dosage levels up to 3.3 mg base/kg/day (approximately 1100 times the recommended human ocular dose). In another study involving 20 rabbit dams, dosed orally up to 2.64 mg base/kg/day, no adverse effects were observed other than a decrease in weight gain during the dosing period, and no treatment related embryolethal or teratogenic effects were observed.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. ALPHAGAN® (ophthalmic solution, 0.2% w/v), submission control 267088, Product Monograph, AbbVie Corporation, (SEP 29, 2022).