


Product Monograph - Canesoral
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic | 01/2026 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Skin | 01/2026 |
| 7 WARNINGS AND PRECAUTIONS, 7.1 Special Populations, 7.1.1 Pregnant Women | 01/2026 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics .............................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ..................................................... 4
4.5 Missed Dose ......................................................................................................... 5
5 OVERDOSAGE .............................................................................................................. 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 5
7 WARNINGS AND PRECAUTIONS .................................................................................. 6
7.1 Special Populations ............................................................................................... 8
7.1.1 Pregnant Women ............................................................................................. 8
7.1.2 Breast-feeding .................................................................................................. 9
7.1.3 Pediatrics .......................................................................................................... 9
8 ADVERSE REACTIONS ................................................................................................ 10
8.1 Adverse Reactions Overview .............................................................................. 10
8.2 Clinical Trial Adverse Reactions .......................................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions ................................................... 11
8.5 Post-Market Adverse Reactions ......................................................................... 11
9 DRUG INTERACTIONS ................................................................................................ 12
9.1 Serious Drug Interactions ................................................................................... 12
9.2 Drug Interactions Overview ............................................................................... 12
9.4 Drug-Drug Interactions ....................................................................................... 12
9.5 Drug-Food Interactions ....................................................................................... 18
9.6 Drug-Herb Interactions ....................................................................................... 18
9.7 Drug-Laboratory Test Interactions ...................................................................... 18
10 CLINICAL PHARMACOLOGY ....................................................................................... 19
10.1 Mechanism of Action .......................................................................................... 19
10.2 Pharmacodynamics ............................................................................................ 19
10.3 Pharmacokinetics ............................................................................................... 20
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 21
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 21
PART II: SCIENTIFIC INFORMATION ....................................................................................... 22
13 PHARMACEUTICAL INFORMATION ............................................................................ 22
14 CLINICAL TRIALS ........................................................................................................ 24
14.1 Trial Design and Study Demographics ................................................................ 24
14.2 Study Results ...................................................................................................... 25
15 MICROBIOLOGY ........................................................................................................ 27
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 31
PATIENT MEDICATION INFORMATION .................................................................................. 38
PATIENT MEDICATION INFORMATION .................................................................................. 43
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
CANESORAL® (fluconazole capsule) is indicated for the single-dose treatment of vaginal candidiasis (yeast infections due to Candida) and is clinically proven to cure most vaginal yeast infections.
CANESORAL® COMBI 1 DAY contains CANESORAL® (fluconazole capsule) and CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole 2%) which is indicated for the topical treatment of external irritation caused by vulvovaginal candidiasis.
1.1 Pediatrics
Pediatrics (>12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of CANESORAL® and CANESORAL® COMBI 1 DAY in pediatric patients has been established. Therefore, Health Canada has authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics).
2 CONTRAINDICATIONS
- CANESORAL® (fluconazole) and CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole) are contraindicated in patients who have shown hypersensitivity to fluconazole, clotrimazole or to any of the excipients used. See the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING section of the product monograph for a complete listing of excipients. There is no information regarding cross hypersensitivity between fluconazole and other azole antifungal agents. Caution should be used by individuals having hypersensitivity to other azoles when using fluconazole.
- Co-administration of terfenadine* is contraindicated in patients receiving fluconazole at multiple doses of 400 mg/day or higher based upon results of a multiple-dose interaction study (see 9 DRUG INTERACTIONS).
- Co-administration of cisapride* is contraindicated in patients receiving fluconazole (see 9 DRUG INTERACTIONS).
- Co-administration of drugs known to prolong the QT interval and which are metabolized via the enzyme CYP3A4 such as amiodarone, erythromycin, pimozide and quinidine are contraindicated in patients receiving fluconazole (see 9 DRUG INTERACTIONS).
*not marketed in Canada
4 DOSAGE AND ADMINISTRATION
4.2 Recommended Dose and Dosage Adjustment
- The recommended dosage of CANESORAL® (fluconazole) for vaginal candidiasis is 150 mg as a single oral dose.
- No dosage adjustment required in hepatic or renal impairment.
Use Canesten Extra Strength External Antifungal Cream (clotrimazole) only in conjunction with CANESORAL® Capsules. The cream should be spread onto the
- irritated area once or twice daily as needed, for up to seven consecutive days.
- Vaginal Candidiasis may be accompanied by irritation in the vaginal area. Therefore, concomitant local treatment with CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM applied to the irritated vaginal area and as far as the anal region twice a day is advisable. CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM applied on the glans penis may prevent re-infection by the partner.
4.5 Missed Dose
Not applicable.
5 OVERDOSAGE
CANESORAL® (fluconazole)
Symptoms: There have been reports of overdosage with fluconazole and in one reported case, a 42-year-old patient infected with human immunodeficiency virus developed hallucinations and exhibited paranoid behaviour after reportedly ingesting 8200 mg of fluconazole. The patient was admitted to the hospital, and his condition resolved within 48 hours.
Treatment: In the event of overdose, symptomatic treatment (with supportive measures and gastric lavage if necessary) may be adequate. Fluconazole is largely excreted in urine. A 3-hour hemodialysis session decreases plasma levels by approximately 50%.
Mice and rats receiving very high doses of fluconazole, whether orally or intravenously, displayed a variety of nonspecific, agonal signs such as decreased activity, ataxia, shallow respiration, ptosis, lacrimation, salivation, urinary incontinence and cyanosis. Death was sometimes preceded by clonic convulsions.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Acute overdosage with topical application of CANESTEN® Cream is unlikely and would not be expected to lead to a life-threatening situation.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Brand Name | Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| CANESORAL® | oral | capsule / 150 mg / fluconazole | colloidal silicon dioxide, D&C Red #7, gelatin, lactose monohydrate, magnesium stearate; pregelatinized starch, propylene glycol, sodium lauryl sulphate and titanium dioxide |
CANESORAL® Capsules are available as hard white gelatin capsules, marked with “CanesOral” in pink colour on the body of the capsule. Each capsule contains 150 mg of fluconazole. Supplied as a unit dose blister pack of 1 capsule.
CANESORAL® COMBI 1 DAY is supplied in a box which contains CANESORAL® and CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM is supplied in a 15 g tube of 2% external vanishing cream.
7 WARNINGS AND PRECAUTIONS
Clinically significant warnings and precautions for CANESORAL® (fluconazole) and CANESTEN® EXTRA STRENGTH EXTERNAL CREAM (clotrimazole) are listed below.
Patients should seek medical advice if they have frequent vaginal infections or if their yeast infection returns in less than 2 months.
While sexual relations may be had during treatment, most couples wait until treatment has finished as the partner could become infected.
CANESORAL® (fluconazole)
General
CANESORAL® (fluconazole) is indicated for single dose only. Some (not all) adverse experiences have been reported in patients following exposure to multiple doses of fluconazole.
The convenience of the single oral dose fluconazole regimen for the treatment of vaginal yeast infections should be weighed against the acceptability of a higher incidence of drug related adverse events with oral fluconazole (26%) versus intravaginal agents (16%) in comparative clinical studies where no difference in efficacy was demonstrated (see 8 ADVERSE REACTIONS).
| Brand Name | Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole) | topical | cream / 2% / clotrimazole | benzyl alcohol, cetostearyl alcohol, cetyl esters wax, octyldodecanol, polysorbate 60, sorbitan monostearate and water. |
Fluconazole administered in combination with ethinyl estradiol- and levonorgestrel-containing oral contraceptives produced an overall mean increase in ethinyl estradiol and levonorgestrel levels; however, in some patients there were decreases up to 47% and 33% of ethinyl estradiol and levonorgestrel levels, respectively (See 9 DRUG INTERACTIONS). The data presently available indicate that the decreases in some individual ethinyl estradiol and levonorgestrel AUC values with fluconazole treatment may be the result of random variation. While there is evidence that fluconazole can inhibit the metabolism of ethinyl estradiol and levonorgestrel, there is no evidence that fluconazole is a net inducer of ethinyl estradiol or levonorgestrel metabolism. The clinical significance of these effects is presently unknown.
Cardiovascular
QT Prolongation:
Some azoles, including fluconazole, have been associated with prolongation of the QT interval on the electrocardiogram. During post-marketing surveillance, there have been very rare cases of QT prolongation and Torsade de Pointes in patients taking fluconazole. These reports included seriously ill patients with multiple confounding risk factors, such as structural heart disease, electrolyte abnormalities and concomitant medications that may have been contributory. Fluconazole should be administered with caution to patients with these potentially proarrhythmic conditions (see 9 DRUG INTERACTIONS and 8 ADVERSE REACTIONS).
Endocrine and Metabolism
Adrenal insufficiency has been reported in patients receiving other azoles (e.g., ketoconazole). Reversible cases of adrenal insufficiency were reported in patients receiving fluconazole or when fluconazole was discontinued (see 9 DRUG INTERACTIONS).
Hepatic/Biliary/Pancreatic
Fluconazole should be administered with caution to patients with liver dysfunction.
In the treatment of systemic infections, multiple doses of fluconazole have been associated with rare cases of serious hepatic toxicity, including fatalities primarily in patients with serious underlying medical conditions. In cases of fluconazole-associated hepatotoxicity, no obvious relationship to total daily dose, duration of therapy, sex or age of the patient has been observed. Fluconazole hepatotoxicity has usually, but not always, been reversible on discontinuation of therapy.
Immune
In rare cases, anaphylaxis and angioedema have been reported in patients using fluconazole.
Skin
In very rare cases, during the treatment of systemic and vaginal infections, patients have developed exfoliative skin disorders (Stevens-Johnson Syndrome, Toxic Epidermal Necrolysis) during treatment with fluconazole.
Drug reaction with eosinophilia and systemic symptoms (DRESS) has been reported.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Ophthalmologic
CANESTEN® Cream is not for ophthalmic use.
Reproductive Health: Female and Male Potential
Fertility
No human studies of the effects of clotrimazole on fertility have been performed; however, animal studies have not demonstrated any effects of the drug on fertility.
Skin
As with all topical agents, skin sensitization may result. Use of CANESTEN® topical preparations should be discontinued should such reactions occur, and appropriate therapy instituted.
7.1 Special Populations
7.1.1 Pregnant Women
CANESORAL® (fluconazole)
Women of childbearing potential
Before initiating treatment, the patient should be informed of the potential risk to the fetus.
Effective contraceptive measures should be considered in women of child-bearing potential and should continue for approximately 1 week (5 to 6 half-lives) after the dose.
Pregnancy
Fluconazole should not be used in pregnant women except in patients with severe or potentially life-threatening fungal infections in whom fluconazole may be used if the anticipated benefit outweighs the possible risk to the fetus.
Observational studies have suggested an increased risk of spontaneous abortion in women treated with fluconazole during the first and/or second trimester compared to women not treated with fluconazole or treated with topical azoles during the same period.
Observational studies have suggested an increased risk of birth defects in women treated with fluconazole during the first trimester.
Data from several thousand pregnant women treated with a cumulative dose of ≤ 150 mg of fluconazole, administered in the first trimester, show no increase in the overall risk of malformations in the foetus. In one large observational cohort study, first trimester exposure to oral fluconazole was associated with a small increased risk of musculoskeletal malformations, corresponding to approximately 1 additional case per 1000 women treated with cumulative doses ≤450 mg compared with women treated with topical azoles and to approximately 4 additional cases per 1000 women treated with cumulative doses over 450 mg. The adjusted relative risk was 1.29 (95% CI 1.05 to 1.58) for 150 mg oral fluconazole and 1.98 (95% CI 1.23 to 3.17) for doses over 450 mg fluconazole.
Available epidemiological studies on cardiac malformations with use of fluconazole during pregnancy provide inconsistent results. However, a meta-analysis of 5 observational studies including several thousand pregnant women exposed to fluconazole during the first trimester finds a 1.8-2 fold increased risk of cardiac malformations when compared to no fluconazole use and/or topical azoles use.
Case reports describe a pattern of birth defects among infants whose mothers were treated with high dose (400-800 mg/day) fluconazole during pregnancy for 3 months or more, in the treatment for coccidioidomycosis (an unapproved indication). The birth defects seen in these infants include brachycephaly, ears dysplasia, giant anterior fontanelles, femoral bowing and radio-humeral synostosis. A causal relationship between fluconazole use and these birth defects is uncertain.
Fluconazole was administered orally to pregnant rabbits during organogenesis in two studies, at 5, 10 and 20 mg/kg and at 5, 25 and 75 mg/kg respectively. Maternal weight gain was impaired at all dose levels, and abortions occurred at 75 mg/kg (approximately 9.4x the maximum recommended human dose); no adverse fetal effects were detected. In several studies in which pregnant rats were treated orally with fluconazole during organogenesis, maternal weight gain was impaired and placental weights were increased at the 25 mg/kg dose. There were no fetal effects at 5 or 10 mg/kg; increases in fetal anatomical variants (supernumerary ribs, renal pelvis dilation) and delays in ossification were observed at 25 and 50 mg/kg and higher doses. At doses ranging from 80 mg/kg to 320 mg/kg (approximately 10-40x the maximum recommended human dose) embryo lethality in rats was increased and fetal abnormalities included wavy ribs, cleft palate, and abnormal craniofacial ossification. These effects are consistent with the inhibition of estrogen synthesis in rats and may be a result of known effects of lowered estrogen on pregnancy, organogenesis, and parturition.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
There are limited amounts of data from the use of clotrimazole in pregnant women. Animal studies do not indicate direct or indirect harmful effects with respect to reproductive toxicity (see 16 NON-CLINICAL TOXICOLOGY, Reproduction and Teratology). Although intravaginal application of clotrimazole has shown negligible absorption from both normal and inflamed human vaginal mucosa, CANESTEN® Cream should not be used in the first trimester of pregnancy unless the physician considers it essential to the welfare of the patient.
7.1.2 Breast-feeding
CANESORAL® (fluconazole)
CANESORAL® is secreted in human breast milk at concentrations similar to plasma, hence its use in nursing mothers is not recommended (see 10.3 Pharmacokinetics).
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Available pharmacodynamic/toxicological studies in animals have shown excretion of clotrimazole/metabolites in milk. Breastfeeding should be discontinued during treatment with clotrimazole.
7.1.3 Pediatrics
CANESORAL® (fluconazole) and CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole) should not be used by girls less than 12 years of age unless advised by a physician.
8 ADVERSE REACTIONS
8.1 Adverse Reactions Overview
The most common treatment-related adverse events reported in adults who received 150 mg single dose fluconazole for vaginal candidiasis are headache (12.9%), nausea (6.7%), abdominal pain (5.6%), and diarrhea (2.7%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
CANESORAL® (fluconazole)
In patients with vaginal candidiasis treated with fluconazole (150 mg) as a single oral dose, the adverse events documented in two controlled North American trials were as follows:
Table 2: Adverse events in patients with vaginal candidiasis treated with fluconazole (150mg) as a single oral dose.
| Percent of Patients With Side Effects | ||||
|---|---|---|---|---|
| Fluconazole (n=448) % | Intravaginal Products (n=422) % | |||
| Drug Related Side Effects | 26.1 | 15.9 | ||
| Nausea | 6.7 | 0.7 | ||
| Abdominal Pain | 5.6 | 1.7 | ||
| Diarrhea | 2.7 | 0.5 | ||
| Dyspepsia | 1.3 | 0.2 | ||
| Headache | 12.9 | 6.6 | ||
| Applicaiton Site Reactions | 0.0 | 4.5 | ||
| Dizziness | 1.3 | 0.0 | ||
| Taste Perversion | 1.3 | 0.0 | ||
| Most of the Reported side effects were mild to moderate in severity. | ||||
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Experimental, therapeutic, and large-scale clinical studies have shown CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM to be well tolerated after topical application.
Immune system disorders: anaphylactic reaction, angioedema, hypersensitivity
Vascular disorder: syncope, hypotension
Respiratory, thoracic and mediastinal disorders: dyspnea
Skin and subcutaneous skin disorders: urticaria, blisters, discomfort/pain, edema, erythema, irritation, peeling/exfoliation, pruritus, rash, stinging/burning sensation
Two of 419 (0.5%) patients treated with a 1% vaginal cream experienced adverse reactions judged to be possibly drug related. These were intercurrent cystitis and vaginal burning. Neither necessitated discontinuation of treatment. None were of serious consequence and no complications occurred.
8.3 Less Common Clinical Trial Adverse Reactions
CANESORAL® (fluconazole)
Occasional allergic reactions including pruritus and urticaria were reported.
8.5 Post-Market Adverse Reactions
CANESORAL® (fluconazole)
In marketing experience of single-dose fluconazole, rare cases of anaphylactic reaction and angioedema have been reported.
In addition, the following adverse experiences have been reported in patients under conditions (e.g. open trials, marketing experience fluconazole) where a causal relationship is uncertain or in patients treated with multiple doses of fluconazole:
Cardiovascular: QT prolongation, Torsade de Pointes (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular, QT Prolongation).
Central and Peripheral Nervous System: seizures.
Dermatologic: alopecia, exfoliative skin disorders including Stevens-Johnson syndrome and toxic epidermal necrolysis (see 7 WARNINGS AND PRECAUTIONS). Drug reactions with eosinophilia and systemic symptoms (DRESS); causal relationship uncertain.
Gastrointestinal: vomiting.
Hematopoietic and Lymphatic: leukopenia including neutropenia and agranulocytosis, thrombocytopenia.
Immunologic: face edema.
General disorders and administration site conditions: urticaria
Liver/Biliary: hepatic failure, hepatitis, hepatocellular necrosis, jaundice.
Metabolic/Nutritional: hypercholesterolaemia, hypertriglyceridaemia, hypokalaemia.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
- Co-administration of terfenadine* is contraindicated in patients receiving fluconazole at multiple doses of 400 mg/day or higher based upon results of a multiple-dose interaction study (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions).
- Co-administration of cisapride* is contraindicated in patients receiving fluconazole (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions).
- Co-administration of drugs known to prolong the QT interval and which are metabolized via the enzyme CYP3A4 such as amiodarone, erythromycin, pimozide and quinidine are contraindicated in patients receiving fluconazole (see 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions).
- Co-administration with sulfonylurea oral hypoglycemic agents such as tolbutamide, glipizide, glyburide may precipitate clinically significant hypoglycemia. One fatality has been reported from hypoglycemia in association with combined fluconazole and glyburide use (see 9.4 Drug-Drug Interactions).
- Co-administration with coumarin-type or indanedione* anticoagulants may increase prothrombin time. Bleeding events have been reported in patients receiving fluconazole and warfarin (see 9.4 Drug-Drug Interactions).
*not marketed in Canada
9.2 Drug Interactions Overview
Fluconazole is a moderate inhibitor of cytochrome P450 (CYP) isoenzymes 2C9 and 3A4. Fluconazole is also a strong inhibitor of the isoenzyme CYP2C19. In addition to the observed /documented interactions mentioned below, there is a risk of increased plasma concentration of other compounds metabolized by CYP2C9, CYP2C19 and CYP3A4 coadministered with fluconazole. Therefore caution should be exercised when using these combinations and the patients should be carefully monitored. The enzyme inhibiting effect of fluconazole persists 4-5 days after discontinuation of fluconazole treatment due to the long half-life of fluconazole.
This product monograph does not list all possible drug-drug interactions; therefore, it is recommended to consult drug interaction databases and the product monographs of any concomitant drugs to determine whether monitoring or dosage adjustments for these drugs are recommended.
9.4 Drug-Drug Interactions
CANESORAL® (fluconazole)
Clinically or potentially significant drug interactions between fluconazole and the following agents/classes have been observed.
ABROCITINIB
Fluconazole (inhibitor of CYP2C19, 2C9, 3A4) increased exposure of abrocitinib active moiety by 155%. If co-administered with fluconazole, adjust the dose of abrocitinib as instructed in the abrocitinib prescribing information.
BENZODIAZEPINES (SHORT ACTING)
Following oral or intravenous administration of midazolam, fluconazole resulted in substantial increases in midazolam concentrations and psychomotor effects. This effect on midazolam appears to be more pronounced following oral administration of fluconazole than with fluconazole administered intravenously. If concomitant benzodiazepine therapy, such as midazolam or triazolam, is necessary in patients being treated with fluconazole, consideration should be given to decreasing the benzodiazepine dosage.
CARBAMAZEPINE
Fluconazole inhibits the metabolism of carbamazepine and an increase in serum carbamazepine of 30% has been observed. There is a risk of developing carbamazepine toxicity. Dosage adjustment of carbamazepine may be necessary depending on concentration measurements/effect.
CIMETIDINE
Absorption of orally administered fluconazole does not appear to be affected by gastric pH. Fluconazole 100 mg was administered as a single oral dose alone and two hours after a single dose of cimetidine 400 mg to six healthy male volunteers. After the administration of cimetidine, there was a significant decrease in fluconazole AUC (area under the plasma concentration-time curve) and Cmax. There was a mean ± SD decrease in fluconazole AUC of 13% ± 11% (range: -3.4 to -31%) and Cmax decreased 19% ± 14% (range: -5 to -40%). However, the administration of cimetidine 600 mg to 900 mg intravenously over a 4-hour period (from 1 hour before to 3 hours after a single oral dose of fluconazole 200 mg) did not affect the bioavailability or pharmacokinetics of fluconazole in 24 healthy male volunteers.
COUMARIN-TYPE OR INDANEDIONE* ANTICOAGULANTS
In a clinical trial, there was a significant increase in prothrombin time response (area under the prothrombin time-time curve) following a single dose of warfarin (15 mg) administered to 13 normal male volunteers following oral fluconazole 200 mg administered daily for 14 days as compared to the administration of warfarin alone. There was a mean ± SD increase in the prothrombin time response (area under the prothrombin time-time curve) of 7% ± 4% (range: -2 to 13%). Mean is based on data from 12 subjects as one of 13 subjects experienced a 2-fold increase in his prothrombin time response.
During the post-marketing experience, as with some azole antifungals, bleeding events (bruising, epistaxis, gastrointestinal bleeding, hematuria, and melena) have been reported, in association with increases in prothrombin time in patients receiving fluconazole concurrently with warfarin.
Prothrombin time may be increased in patients receiving concomitant fluconazole and coumarin-type or indanedione* anticoagulants. Dose adjustment of these anticoagulants may be necessary.
*Not marketed in Canada
CYCLOSPORINE
Cyclosporine AUC and Cmax were determined before and after the administration of fluconazole 200 mg daily for 14 days in eight renal transplant patients who had been on cyclosporine therapy for at least 6 months and on a stable cyclosporine dose for at least 6 weeks. There was a significant increase in cyclosporine AUC, Cmax, Cmin (24-hour concentration), and a significant reduction in apparent oral clearance following the administration of fluconazole. The mean ± SD increase in AUC was 92% ± 43% (range: 18 to 147%). The Cmax increased 60% ± 48% range (range: -5 to 133%). The Cmin increased 157% ± 96% (range: 33 to 360%). The apparent oral clearance decreased 45% ± 15% (range: -15 to -60%). Fluconazole administered at 100 mg daily dose does not affect cyclosporine pharmacokinetic levels in patients with bone marrow transplants. Fluconazole may significantly increase cyclosporine levels in renal transplant patients with or without renal impairment.
DRUGS PROLONGING THE QTc INTERVAL:
The use of fluconazole in patients concurrently taking drugs metabolized by the Cytochrome P-450 system may be associated with elevations in the serum levels of these drugs.
Astemizole*: Definitive interaction studies with fluconazole have not been conducted. The use of fluconazole may be associated with elevations in serum levels of astemizole. Caution should be used when coadministering fluconazole with astemizole. Patients should be carefully monitored.
Cisapride*: There have been reports of cardiac events including torsade de pointes in patients to whom fluconazole and cisapride were coadministered. A controlled study found that concomitant fluconazole 200 mg once daily and cisapride 20 mg four times a day yielded a significant increase in cisapride plasma levels and prolongation of QTc interval. Co-administration of cisapride is contraindicated in patients receiving fluconazole. (see 2 CONTRAINDICATIONS).
Terfenadine*: Because of the occurrence of serious cardiac dysrhythmias secondary to prolongation of the QTc interval in patients receiving azole antifungals in conjunction with terfenadine, interaction studies have been performed. In one study, 6 healthy volunteers received terfenadine 60 mg BID for 15 days. Fluconazole 200 mg was administered daily from days 9 through 15. Fluconazole did not affect terfenadine plasma concentrations. Terfenadine acid metabolite AUC increased 36% ± 36% (range: 7 to 102%) from day 8 to day 15 with the concomitant administration of fluconazole. There was no change in cardiac repolarization as measured by Holter QTc intervals. However, another study at a 400 mg and 800 mg daily dose of fluconazole demonstrated that fluconazole taken in doses of 400 mg per day or greater significantly increases plasma levels of terfenadine when taken concomitantly. Therefore the combined use of fluconazole at doses of 400 mg or higher with terfenadine is contraindicated (see 2 CONTRAINDICATIONS). Patients should be carefully monitored if they are being concurrently prescribed fluconazole at multiple doses lower than 400 mg/day with terfenadine.
*not marketed in Canada
Pimozide: Although not studied in vitro or in vivo, concomitant administration of fluconazole with pimozide may result in inhibition of pimozide metabolism. Increased pimozide plasma concentrations can lead to QT prolongation and rare occurrences of torsade de pointes. Coadministration of fluconazole and pimozide is contraindicated (see 2 CONTRAINDICATIONS).
Quinidine: Although not studied in vitro or in vivo, concomitant administration of fluconazole with quinidine may result in inhibition of quinidine metabolism. Use of quinidine has been associated with QT prolongation and rare occurrences of Torsades de Pointes. Coadministration of fluconazole and quinidine is contraindicated (see 2 CONTRAINDICATIONS).
Erythromycin: Concomitant use of fluconazole and erythromycin has the potential to increase the risk of cardiotoxicity (prolonged QT interval, torsade de pointes) and consequently sudden heart death. Coadministration of fluconazole and erythromycin is contraindicated (see 2 CONTRAINDICATIONS).
Amiodarone: Concomitant administration of fluconazole with amiodarone may increase QT prolongation. Caution must be exercised if the concomitant use of fluconazole and amiodarone is necessary, notably with high-dose fluconazole (800 mg) (see 2 CONTRAINDICATIONS).
Lemborexant: Concomitant administration of fluconazole increased lemborexant Cmax and AUC by approximately 1.6- and 4.2-fold, respectively which is expected to increase risk of adverse reactions, such as somnolence. Avoid concomitant use of lemborexant.
HMG-CoA reductase inhibitors
The risk of myopathy and rhabdomyolysis increases (dose-dependent) when fluconazole is coadministered with HMG-CoA reductase inhibitors metabolized through CYP3A4, such as atorvastatin and simvastatin, or through CYP2C9, such as Fluvastatin (decreased hepatic metabolism of the statin). If concomitant therapy is necessary, the patient should be observed for symptoms of myopathy and rhabdomyolysis and creatine kinase should be monitored. HMG-CoA reductase inhibitors should be discontinued if a marked increase in creatine kinase is observed or myopathy/rhabdomyolysis is diagnosed or suspected. Lower doses of HMG-CoA reductase inhibitors may be necessary as instructed in the statins prescribing information.
HYDROCHLOROTHIAZIDE
Concomitant oral administration of 100 mg fluconazole and 50 mg hydro-chlorothiazide for 10 days in 13 normal volunteers resulted in a significant increase in fluconazole AUC and Cmax compared to fluconazole given alone. There was a mean ± SD increase in fluconazole AUC and Cmax of 45% ± 31% (range: 19 to 114%) and 43% ± 31% (range: 19 to 122%), respectively. These changes are attributed to a mean ± SD reduction in renal clearance of 30% ± 12% (range -10 to -50%)
IVACAFTOR (alone or combined with drugs in the same therapeutic class)
Coadministration with ivacaftor, a cystic fibrosis transmembrane conductance regulator (CFTR) potentiator, increased ivacaftor exposure by 3-fold. A reduction of the ivacaftor (alone or combined) dose is necessary as instructed in the ivacaftor (alone or combined) prescribing information.
IBRUTINIB
Moderate inhibitors of CYP3A4 such as fluconazole increase plasma ibrutinib concentrations and may increase risk of toxicity. If the combination cannot be avoided, reduce the dose of ibrutinib as instructed in ibrutinib Product Monograph and provide close clinical monitoring.
LURASIDONE
Moderate inhibitors of CYP3A4 such as fluconazole may increase lurasidone plasma concentrations. If concomitant use cannot be avoided, reduce the dose of lurasidone as instructed in the lurasidone prescribing information.
NON-STEROIDAL ANTI-INFLAMMATORY DRUGS
Flurbiprofen, Ibuprofen, Meloxicam, Diclofenac: The Cmax and AUC of flurbiprofen were increased by 23% and 81%, respectively, when coadministered with fluconazole compared to administration of flurbiprofen alone. Similarly, the Cmax and AUC of the pharmacologically active isomer [S-(+)-ibuprofen] were increased by 15% and 82%, respectively, when fluconazole was coadministered with racemic ibuprofen (400 mg) compared to administration of racemic ibuprofen alone.
Although not specifically studied, fluconazole has the potential to increase the systemic exposure of other non-steroidal anti-inflammatory drugs (NSAIDs) that are metabolized by CYP2C9 (e.g., meloxicam, diclofenac). Frequent monitoring for adverse events and toxicity related to NSAIDs is recommended. Adjustment of dosage of NSAIDs may be needed.
Celecoxib: During concomitant treatment with fluconazole (200 mg daily) and celecoxib (200 mg) the celecoxib Cmax and AUC increased by 68% and 134%, respectively. Half of the celecoxib dose may be necessary when combined with fluconazole.
ORAL CONTRACEPTIVES
Oral contraceptives were administered as a single dose both before and after the oral administration of fluconazole 50 mg once daily for 10 days in 10 healthy women. There was no significant difference in ethinyl estradiol or levonorgestrel AUC after the administration of fluconazole. The mean increase in ethinyl estradiol AUC was 6% (range: -47 to 108%) and levonorgestrel AUC increased 17% (range: -33 to 141%).
Twenty-five normal females received daily doses of both 200 mg fluconazole or placebo for two, ten-day periods. The treatment cycles were one month apart with all subjects receiving fluconazole during one cycle and placebo during the other. The order of study treatment was random. Single doses of an oral contraceptive tablet containing levonorgestrel and ethinyl estradiol were administered on the final treatment day (day 10) of both cycles. Following administration of 200 mg of fluconazole, the mean percentage increase of AUC for levonorgestrel compared to placebo was 25% (range: -12 to 82%) and the mean percentage increase for ethinyl estradiol compared to placebo was 38% (range: -11 to 101%). Both of these increases were statistically significantly different from placebo.
ORAL HYPOGLYCEMICS
The effects of fluconazole on the pharmacokinetics of the sulfonylurea oral hypoglycemic agents tolbutamide, glipizide, and glyburide were evaluated in three placebo-controlled studies in normal volunteers. All subjects received the sulfonylurea alone as a single dose and again as a single dose following the administration of fluconazole 100 mg daily for 7 days. In these three studies, 22/46 (47.8%) of fluconazole-treated patients and 9/22 (40.1%) of placebo-treated patients experienced symptoms consistent with hypoglycemia.
Tolbutamide: In 13 normal male volunteers, there was a significant increase in tolbutamide (500 mg single dose) AUC and Cmax following the administration of fluconazole. There was a mean ± SD increase in tolbutamide AUC of 26% ± 9% (range: 12 to 39%). Tolbutamide Cmax increased 11% ± 9% (range: 6 to 27%).
Glipizide: The AUC and Cmax of glipizide (2.5 mg single dose) were significantly increased following the administration of fluconazole in 13 normal male volunteers. There was a mean ± SD increase in AUC of 49% ± 13% (range: 27 to 73%) and an increase in Cmax of 19% ± 23% (range: -11 to 79%).
Glyburide: The AUC and Cmax of glyburide (5 mg single dose) were significantly increased following the administration of fluconazole in 20 normal male volunteers. There was a mean ± SD increase in AUC of 44% ± 29% (range: -13 to 115%) and Cmax increased 19% ± 19% (range: -23 to 62%). Five subjects required oral glucose following the ingestion of glyburide after 7 days of fluconazole administration.
Clinically significant hypoglycemia may be precipitated by the use of fluconazole with oral hypoglycemic agents; one fatality has been reported from hypoglycemia in association with combined fluconazole and glyburide use. Fluconazole reduces the metabolism of tolbutamide, glyburide, and glipizide and increases the plasma concentration of these agents.
PHENYTOIN
Fluconazole increases the plasma concentrations of phenytoin. Phenytoin AUC was determined after 4 days of phenytoin dosing (200 mg daily, orally for 3 days, followed by 250 mg intravenously for one dose) both with and without the administration of fluconazole (oral fluconazole 200 mg daily for 16 days) in 10 normal male volunteers. There was a significant increase in phenytoin AUC. The mean ± SD increase in phenytoin AUC was 88% ± 68% (range: 16 to 247%). The absolute magnitude of this interaction is unknown because of the intrinsically non-linear disposition of phenytoin.
PREDNISONE
There was a case report that a liver-transplanted patient treated with prednisone developed acute adrenal-cortex insufficiency when a 3-month therapy with fluconazole was discontinued. The discontinuation of fluconazole presumably caused an enhanced CYP3A4 activity which led to increased metabolism of prednisone. Patients on long-term treatment with fluconazole and prednisone should be carefully monitored for adrenal cortex insufficiency when fluconazole is discontinued.
RIFABUTIN
There have been reports that an interaction exists when fluconazole is administered concomitantly with rifabutin, leading to increased serum levels of rifabutin. There have been reports of uveitis in patients to whom fluconazole and rifabutin were coadministered.
RIFAMPIN
Administration of a single oral 200 mg dose of fluconazole after 15 days of rifampin administered as 600 mg daily in 8 healthy male volunteers resulted in a significant decrease in fluconazole AUC and a significant increase in apparent oral clearance of fluconazole. There was a mean ± SD reduction in fluconazole AUC of 23% ± 9% (range: -13 to -42%). Apparent oral clearance of fluconazole increased 32% ± 17% (range: 16 to 72%). Fluconazole half-life decreased from 33.4 ± 4.4 hours to 26.8 ± 3.9 hours.
Rifampin enhances the metabolism of concurrently administered fluconazole.
TACROLIMUS
There have been reports that an interaction exists when fluconazole is administered concomitantly with tacrolimus, leading to increased serum levels of tacrolimus. There have been reports of nephrotoxicity in patients to whom fluconazole and tacrolimus were coadministered.
THEOPHYLLINE
The pharmacokinetics of theophylline were determined from a single intravenous dose of aminophylline (6 mg/kg) before and after the oral administration of fluconazole 200 mg daily for 14 days in 16 normal male volunteers. There were significant increases in theophylline AUC, Cmax and half-life with a corresponding decrease in clearance. The mean ± SD theophylline AUC increased 21% ± 16% (range: -5 to 48%). The Cmax increased 13% ± 17% (range: -13 to 40%). Theophylline clearance decreased 16% ± 11% (range: -32 to 5%). The half-life of theophylline increased from 6.6 ± 1.7 hours to 7.9 ± 1.5 hours.
TOFACITINIB Exposure of tofacitinib is increased when tofacitinib is co-administered with medications that result in both moderate inhibition of CYP3A4 and strong inhibition of CYP2C19 (e.g. fluconazole). Therefore, it is recommended to reduce tofacitinib dose to 5 mg once daily when it is combined with these drugs.
TOLVAPTAN
Exposure to tolvaptan is significantly increased (200% in AUC; 80% in Cmax) when tolvaptan, a CYP3A4 substrate, is co-administered with fluconazole, a moderate CYP3A4 inhibitor, with risk of significant increase in adverse effects particularly significant diuresis, dehydration and acute renal failure. In case of concomitant use, the tolvaptan dose should be reduced and the patient managed cautiously.
Vinca alkaloids
Although not studied, fluconazole may increase the plasma levels of the vinca alkaloids (e.g., vincristine and vinblastine) and lead to neurotoxicity, which is possibly due to an inhibitory effect on CYP3A4.
ZIDOVUDINE
Plasma zidovudine concentrations were determined on two occasions (before and following fluconazole 200 mg daily for 15 days) in 13 volunteers with AIDS or ARC who were on a stable zidovudine dose for at least two weeks. There was a significant increase in zidovudine AUC following the administration of fluconazole. The mean ± SD increase in AUC was 20% ± 32% (range: -27 to 104%). The metabolite, GZDV, to parent drug ratio significantly decreased after the administration of fluconazole, from 7.6 ± 3.6 to 5.7 ± 2.2.
DRUGS EXHIBITING NO SIGNIFICANT PHARMACOKINETIC INTERACTIONS WITH FLUCONAZOLE:
Antacids: Administration of Maalox® (20 mL) to 14 normal male volunteers immediately prior to a single dose of fluconazole 100 mg had no effect on the absorption or elimination of fluconazole.
Interaction studies with other medications have not been conducted, but such interactions may occur.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Concomitant medication with vaginal Clotrimazole and oral tacrolimus/ sirolimus (immunosuppressants) might lead to increased tacrolimus/sirolimus plasma levels. Patients should thus be thoroughly monitored for symptoms of tacrolimus/ sirolimus overdosage.
9.5 Drug-Food Interactions
Interactions with foods have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
CANESORAL® (fluconazole)
Fluconazole is a highly selective inhibitor of fungal cytochrome P-450 sterol C-14-alpha-demethylation. Mammalian cell demethylation is much less sensitive to fluconazole inhibition. The subsequent loss of normal sterols correlates with the accumulation of 14-beta-methyl sterols in fungi and may be responsible for the fungistatic activity of fluconazole.
Its primary mode of action is the inhibition of fungal cytochrome P-450-mediated 14-alpha-lanosterol demethylation, an essential step in fungal ergosterol biosynthesis. The accumulation of 14-alpha-methyl sterols correlates with the subsequent loss of ergosterol in the fungal cell membrane and may be responsible for the antifungal activity of fluconazole. Fluconazole has been shown to be more selective for fungal cytochrome P-450 enzymes than for various mammalian cytochrome P-450 enzyme systems.
Fluconazole is highly specific for fungal cytochrome P-450 dependent enzymes. Fluconazole 50 mg daily given up to 28 days has been shown not to affect testosterone plasma concentrations in males or steroid concentrations in females of child-bearing age. Fluconazole 200 mg to 400 mg daily has no clinically significant effect on endogenous steroid levels or on adrenocorticotropic hormone (ACTH) stimulated response in healthy male volunteers. Interaction studies with antipyrine indicate that single or multiple doses of fluconazole 50 mg do not affect its metabolism.
Pharmacokinetic/pharmacodynamic relationship
In animal studies, there is a correlation between MIC values and efficacy against experimental mycoses due to Candida spp. In clinical studies, there is an almost 1:1 linear relationship between the AUC and the dose of fluconazole. There is also a direct though imperfect relationship between the AUC or dose and a successful clinical response of oral candidosis and to a lesser extent candidaemia to treatment. Similarly, cure is less likely for infections caused by strains with a higher fluconazole MIC.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole) acts primarily by damaging the permeability barrier in the cell membrane of fungi. CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM brings about inhibition of ergosterol biosynthesis, an essential constituent of fungal cell membranes. If ergosterol synthesis is completely or partially inhibited, the cell is no longer able to construct an intact cell membrane. This leads to death of the fungus.
Exposure of Candida albicans to clotrimazole causes leakage of intracellular phosphorus compounds into the ambient medium with a concomitant breakdown of cellular nucleic acids and potassium eflux. The onset of these events is rapid and extensive after exposure of the organism to the drug, and causes a time-dependent and concentration-dependent inhibition of fungal growth.
10.2 Pharmacodynamics
CANESORAL® (fluconazole)
The effects of fluconazole on the metabolism of carbohydrates, lipids, adrenal and gonadal hormones were assessed. In normal volunteers, fluconazole administration at doses ranging from 200 to 400 mg once daily for up to 14 days was associated with small and inconsistent effects on testosterone concentrations, endogenous corticosteroid concentrations, and the adrenocorticotropic hormone (ACTH) stimulated cortisol response. In addition, fluconazole appears to have no clinically significant effects on carbohydrate or lipid metabolism in man.
10.3 Pharmacokinetics
CANESORAL® (fluconazole)
Fluconazole is a polar bis-triazole antifungal drug. Studies have shown that fluconazole exhibits specificity as an inhibitor of the fungal as opposed to mammalian cytochrome P-450 mediated reactions, including those involved in steroid biosynthesis and drug metabolism. Many of the clinical advantages of fluconazole are a result of its unique pharmacokinetic properties.
Absorption: The pharmacokinetic properties of fluconazole are similar following administration by the intravenous or oral routes and do not appear to be affected by gastric pH. In normal volunteers, the bioavailability of orally administered fluconazole is over 90% compared with intravenous administration. Essentially all of the administered drug reaches systemic circulation; thus, there is no evidence of first-pass metabolism of the drug. In addition, no adjustment in dosage is necessary when changing from p.o. to i.v. or vice versa.
Peak plasma concentrations (Cmax) in fasted normal volunteers occur rapidly following oral administration, usually between 1 and 2 hours of dosing with a terminal plasma elimination half-life of approximately 30 hours (range 20-50 hours) after oral administration. The long plasma elimination half-life provides the basis for once daily dosing with fluconazole in the treatment of fungal infections.
In fasted normal volunteers, administration of a single oral 150 mg dose of fluconazole produced a mean Cmax of 2.70 mcg/mL (range: 1.91 to 3.70 mcg/mL).
In normal volunteers, oral bioavailability as measured by Cmax and AUC was not affected by food when fluconazole was administered as a single 50 mg capsule; however, Tmax was doubled.
A pharmacokinetic study in 10 lactating women, who temporarily or permanently stopped breast-feeding their infant, evaluated fluconazole concentrations in plasma and breast milk for 48 hours following a single 150 mg dose of Diflucan. Fluconazole was detected in breast milk at an average concentration of approximately 98% of those in maternal plasma. The mean peak breast milk concentration was 2.61 mg/L at 5.2 hours post-dose.
Distribution: The apparent volume of distribution of fluconazole approximates that of total body water. Plasma protein binding is low (11-12%) and is constant over the concentration range tested (0.1 mg/L to 10 mg/L). This degree of protein binding is not clinically meaningful.
A single oral 150 mg dose of fluconazole administered to 27 patients penetrated into vaginal tissue, resulting in tissue: plasma ratios ranging from 0.94 to 1.14 over the first 48 hours following dosing.
A single oral 150 mg dose of fluconazole administered to 14 patients penetrated into vaginal fluid, resulting in fluid: plasma ratios ranging from 0.36 to 0.71 over the first 72 hours following dosing.
Metabolism and Excretion: Fluconazole is cleared primarily by renal excretion, with approximately 80% of the administered dose appearing in the urine as unchanged drug. Following administration of radiolabeled fluconazole, greater than 90% of the radioactivity is excreted in the urine. Approximately 11% of the radioactivity in urine is due to metabolites. An additional 2% of the total radioactivity is excreted in feces.
The pharmacokinetics of fluconazole do not appear to be affected by age alone but are markedly affected by reduction in renal function. There is an inverse relationship between the elimination half-life and creatinine clearance. There is no need to adjust single dose therapy for vaginal candidiasis because of impaired renal function.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Pharmacokinetic investigations after vaginal application have shown that only a small amount of clotrimazole (3-10%) is absorbed. Due to the rapid hepatic metabolization of absorbed clotrimazole into pharmacologically active metabolites, the resulting peak plasma concentrations of clotrimazole after vaginal application of a 500 mg dose were less than 10 ng/ml, suggesting that clotrimazole applied intravaginally is unlikely to lead to measurable systemic effects or side effects.
The pharmacokinetics of topically applied clotrimazole in human subjects have been evaluated in studies that were conducted on an inpatient basis in a total of 9 volunteer subjects from the Dermatologic Clinic of the Wup-peral city Hospital who reported on the penetration of radioactive clotrimazole 1% cream and 1% solution into intact and acutely inflamed skin. Six hours after application of the drug, the concentration of clotrimazole found in skin layers varied from 100 mcg/cm3 in the stratum corneum to 0.5 to 1.0 mcg/cm3 in the stratum reticulare and <0.1 mcg/cm3 in the subcutis. No measurable amount of radioactivity (0.001 mcg/mL) was found in the serum within 48 hours after application of 0.5 mL of the solution or 0.8 g of the cream.
11 STORAGE, STABILITY AND DISPOSAL
CANESORAL® (fluconazole) should be stored at room temperature, between 15 - 30°C.
CANESTEN ® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole) should be stored at room temperature, between 15 - 30°C.
12 SPECIAL HANDLING INSTRUCTIONS
This information is not available for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: fluconazole
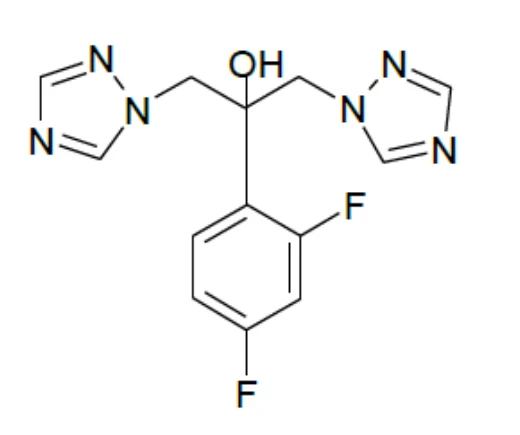
Chemical name: 2-(2,4-difluorophenyl)-1,3-bis(1H-1,2,4-triazol-l-yl)-2-propanol
Molecular formula and molecular mass: C13H12F2N6O, 306.3
Structural formula:
Physicochemical properties:
Description: Fluconazole is a white to off-white crystalline powder.
Solubility (mg/mL solvent):
| Solvents | Solubility at 23oC in % w/v |
| Water | 0.5 |
| Aqueous 0.1 N HCl | 1.4 |
| Aqueous 0.1 N NaOH | 0.5 |
| Chloroform | 3.1 |
| Acetone | 4.0 |
| Isopropanol | 0.8 |
| Methanol | 25.0 |
| Ethanol | 2.5 |
| h-hexane | 0.1 |
| Methanolic 0.01 N HCl | 30.5 |
Melting Range: 136°C to 140°C
pKa: 1.68 ± 0.07 at 24°C
pH:
| pH | Solubility (mg/mL) |
| 1.2 | 12.3 |
| 6.0 | 2.5 |
| 8.0 | 4.8 |
Drug Substance
Proper name: clotrimazole
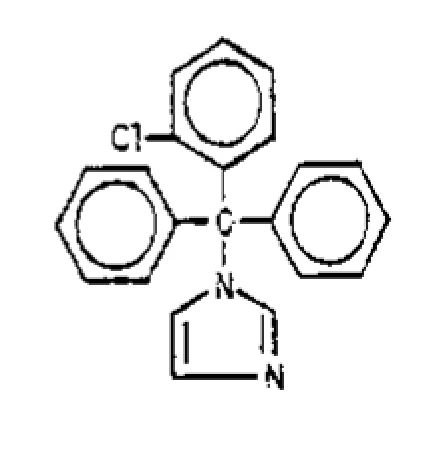
Chemical name: 1-(o-chloro-αα-diphenylbenzyl) imidazole
Molecular formula and molecular mass: C22H17CIN2, 344.84
Structural formula:
Physicochemical properties: Clotrimazole is a white to pale yellow, crystalline, weakly alkaline substance, M.P. 145°C, soluble in acetone, chloroform and ethanol, and practically insoluble in water. It forms stable salts with both inorganic and organic acids. It is not photosensitive but slightly hygroscopic and may by hydrolyzed in acid media.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
The following studies assessed fluconazole 150mg single dose for the treatment and cure of vaginal candidiasis. A total of 13 studies are presented below.
Table 3 - Summary of patient demographics for clinical trials in treatment and cure of vaginal candidiasis.
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Single-Dose Fluconazole Compared to Single-Dose Intravaginal Clotrimazole | RD, O, C | Fluconazole 150mg po sd | 23 | 15-39 years | Females with VC |
| Single-Dose Fluconazole Compared to 3-Day Clotrimazole | RD, C, MC | Fluconazole 150mg po sd | 188 | 32.1 years | Females with VC |
| A clinical efficacy and tolerability in Vulvovaginal Mycoses | RD, SB, PL | Fluconazole 150mg po sd | 154 | Unk | Females with VC |
| A comparative effectiveness study in vaginal candidiasis | O, C | Fluconazole 150mg po sd | 50 | 18-54 years | Females with VC |
| A comparative effectiveness study of antifungal regimens in vaginal candidiasis | O, C | Fluconazole 150mg po sd | 50 | 17-55 years | Females with VC |
| A multicenter study on single-dose oral fluconazole in vaginal candidiasis,1988 | O | Fluconazole 150mg po sd | 180 | 17-67 years | Females with VC |
| A comparative effectiveness and safety study in vulvovaginal candidiasis | RD, SB | Fluconazole 150mg po sd | 53 | 26-43 years | Females with VC |
| Efficacy and safety of Fluconazole in vaginal candidiasis | O, MC | Fluconazole 150mg po sd | 1017 | 17-65 years | Females with VC |
| Single-dose oral fluconazole versus topical clotrimazole in Candida vaginitis | RD, SB, MC, C | Fluconazole 150mg po sd | 218 | 18-63 years | Females with VC |
| Shorter Treatment for vaginal candidosis | RD, O, C | Fluconazole 150mg po sd | 54 | 18-54 years | Females with VC |
| Single-dose oral fluconazole versus single-dose topical miconazole in acute vulvovaginal candidosis | RD, DB, DD, PL | Fluconazole 150mg po sd | 43 | 18-60 years | Females with VC |
| Single-dose oral fluconazole versus single-dose topical clotrimazole in vaginal candidosis | RD, MC, C | Fluconazole 150mg po sd | 243 | 18-65 years | Females with VC |
| Comparison of clotrimazole, fluconazole, and itraconazole in vaginal candidiasis | RD, C | Fluconazole 150mg po sd | 72 | 27.3 years | Females with VC |
14.2 Study Results
Table 4 - Results of study in treatment and cure of vaginal candidiasis
| Study # | Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
|---|---|---|---|
| Study # | Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
| Study # | Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
| Single-Dose Fluconazole Compared to Single-Dose Intravaginal Clotrimazole | CC & MC 8 days CC & MC 32 days | Fluconazole 87% 87% | Clotrimazole 75% P=0.05 60% P=0.5 |
| Single-Dose Fluconazole Compared to 3-Day Clotrimazole | CC 5-16 days CC 27-62 days MC 5-16 days MC 27-62 days | Fluconazole 99% 93% 85% 72% | Clotrimazole 97% P=0.12 84% P=0.02 81% P=0.42 62% P=0.07 |
| A clinical efficacy and tolerability in Vulvovaginal Mycoses | MC 14 days MC & CC 14 days | Fluconazole 76.0% 59.1% | Clotrimazole Vaginal cream Vaginal tablet 73.9% NS 80.1% NS 60.5% NS 65.8% NS |
| A comparative effectiveness study in vaginal candidiasis | CC 5-15 days CC 30-60 days MC 5-15 days | Fluconazole 80% 76% 76% | 100mg intravaginal clotrimazole 72% NS 58% NS 72% NS |
| MC 30-60 days | 70% | 60% NS | |
| A comparative effectiveness study of antifungal regimens in vaginal candidiasis | CC 5-15 days CC 30-60 days MC 5-15 days MC 30-60 days | Fluconazole 80% 76% 76% 70% | Itraconazole Clotrimazole 84% 72% NS 78% 58% NS 80% 72% NS 74% 60% NS |
| A multicenter study on single-dose oral fluconazole in vaginal candidiasis | CC 5-16 days CC 27-62 days MC 5-16 days MC 27-62 days | Fluconazole 97% 88% 94% 73% | Non-comparative study |
| A comparative effectiveness and safety study in vulvovaginal candidiasis | CC 7 days CC 28 days MC 7 days MC 28 days | Fluconazole 88.7% 69.8% 79.2% 60.4% | Clotrimazole 90% NS 68% NS 80% NS 66% NS |
| Efficacy and safety of Fluconazole in vaginal candidiasis | CC | Fluconazole 94.7% | Non-comparative study |
| Single-dose oral fluconazole versus topical clotrimazole in Candida vaginitis | CC 14 days CC 35 days MC 14 days MC 35 days | Fluconazole 94% 75% 77% 63% | Clotrimazole 97% P=0.307 75% P=0.890 72% P=0.332 57% P=0.327 |
| Shorter Treatment for vaginal candidosis | CC 7 days MC 7 days MC 30 days | Fluconazole 100% 83% 71% | Miconazole 100% NS 89% NS 77% NS |
| Single-dose oral fluconazole versus single-dose topical miconazole in acute vulvovaginal candidosis | CC 6-10 days CC 22-44 days MC 6-10 days MC 22-44 days | Fluconazole 81% 86% 98% 74% | Miconazole 78% NS 80% NS 96% NS 82% NS |
| Single-dose oral fluconazole versus single-dose topical clotrimazole in vaginal candidosis | MC 7 days MC 28 days | Fluconazole 82% 75% | Clotrimazole 76% NS 72% NS |
| Comparison of clotrimazole, fluconazole, and itraconazole in vaginal candidiasis | CC 7-10 days MC 7-10 days | Fluconazole 62% 83% | Itraconazole Clotrimazole 80% P=0.032 80% P=0.027 96% P=0.024 95% P=0.033 |
CC: clinical cure, MC: mycological cure, NS: not significant
15 MICROBIOLOGY
CANESORAL® (fluconazole)
Fluconazole is a polar bis-triazole antifungal agent which exhibits fungistatic activity in vitro against a variety of fungi and yeasts; it also exhibits fungistatic activity in vivo against a broad range of systemic and superficial fungal infections.
In common with other azole antifungal agents, most fungi show a higher apparent sensitivity to fluconazole in vivo than in vitro. Both orally and intravenously administered fluconazole was active in a variety of animal fungal infection models. Activity has been demonstrated against opportunistic mycoses, such as infections with Candida spp. including systemic candidiasis and in immunocompromised animals; with Cryptococcus neoformans, including intracranial infections; with Aspergillus spp., including systemic infections in immunocompromised animals; with Microsporum spp.; and with Trichophyton spp. Fluconazole has also been shown to be active in animal models of endemic mycoses, including infections with Blastomyces dermatitidis; with Coccidioides immitis; including intracranial infection; and with Histoplasma capsulatum in normal and immunosuppressed animals.
In Vitro Studies
In vitro, fluconazole displays antifungal activity against most clinically common Candida species (including C. albicans, C. parapsilosis, C. tropicalis). MIC (minimal inhibitory concentration)s for C. glabrata and C. guilliermondii tend to be higher, while C. krusei is intrinsically resistant to fluconazole. The recently emerging species C. auris tends to be relatively resistant to fluconazole.
Fluconazole also exhibits activity in vitro against Cryptococcus neoformans and Cryptococcus. gattii as well as the endemic moulds Blastomyces dermatiditis, Coccidioides immitis, Histoplasma capsulatum and Paracoccidioides brasiliensis.
The clinical relevance of in vitro results obtained with azoles is unknown since MIC can vary greatly depending on the methods and medium used. However, in a defined medium the geometric mean MIC of fluconazole for most Candida species lies between 0.5 and 1.5 mcg /mL. Fluconazole is apparently less potent against dermatophytes and other filamentous fungi although good in vivo activity against these organisms has been demonstrated in animal models. (See Table 5)
The mean MIC* (ug/mL) and MIC range of fluconazole for various pathogenic fungi in a defined medium**
Table 5 – In-Vitro MIC results of fluconazole for various Fungi strains.
| Strains | Number of Isolates | Fluconazole MIC | Range MIC |
| Candida albicans | 159 | 0.39 | 0.1 - 1.56 |
| Candida glabrata | 3 | 1.9 | 1.56 - 3.12 |
| Candida guilliermondii | 3 | 0.62 | 0.39 - 0.78 |
| Candida krusei | 10 | >25 | >25 |
| Candida parapsilosis | 19 | 1.0 | 0.39 - 3.1 |
| Candida pseudotropicalis | 6 | 0.19 | 0.04 - 0.39 |
| Candida tropicalis | 16 | 1.42 | 0.19 - 3.12 |
| Cryptococcus neoformans | 5 | 1.25 | 0.39 - 6.25 |
| Rhodotorula glutinis | 1 | 25 | - |
| Microsporum canis | 4 | 9.4 | 6.25 - 12.5 |
| Microsporum gypseum | 1 | 50 | - |
| Trichophyton mentagrophytes | 21 | >100 | 25 - >100 |
| Trichophyton rubrum | 29 | 39 | 12.5 - 100 |
| Trichophyton soudanense | 2 | 100 | 100 - >100 |
| Trichophyton tonsurans | 4 | 42 | 12.5 - 100 |
| Trichophyton verrucosum | 3 | 37.5 | 12.5 - 50 |
| Aspergillus flavus | 3 | >100 | >100 |
| Aspergillus fumigatus | 7 | >100 | >100 |
| Aspergillus niger | 5 | >100 | >100 |
| Aspergillus terreus | 4 | >100 | >100 |
*Values where 3 or more organisms are used are geometric means.
**Defined tissue culture medium consists of Eagles minimal medium with Earle’s salts, yeast carbon base and phosphate buffer, pH 7.5, with or without agar.
In Vivo Studies
Vaginal Candidosis in Predisposed Mice and Rats:
A vaginal C. albicans infection, induced in mice or ovariectomized rats predisposed with estradiol benzoate, was treated orally with a single dose immediately post-infection (prophylactic) or once daily for 3 days starting 72 h. post-infection (therapeutic). Efficacy was measured as percentage cure compared with untreated controls. In both models in mice or in rats, fluconazole (CD50's 2.7 and 4.4 mg/kg, respectively, in mice and 2.9 and 2.1 mg/kg, respectively, in rats) was at least 5 to 10 times more effective than ketoconazole (CD50's 32 and >50 mg/kg, respectively, in mice and 32 and 12.5 mg/kg, respectively, in rats) in this local infection.
Development of Resistance and Cross-Resistance to Fluconazole
Development of fungal resistance to fluconazole and effects of long-term administration of fluconazole on normal flora have not been systematically investigated.
Significant fungistatic activity of fluconazole was observed against ketoconazole-resistant Candida albicans in a neutropenic rabbit model although doses of the order of 80 mg/kg were required. In another study, however, a strain of Candida albicans isolated from a patient with chronic mucocutaneous candidosis who had relapsed during treatment with ketoconazole was not only cross-resistant to all azole antifungals in vitro but also in animal models in vivo.
High grade azole resistance appears to be cross-reactive in vivo against all other imidazole and triazole antifungal drugs.
The clinical correlation of these data has not been precisely established at this time.
Mechanisms of resistance
In usually susceptible species of Candida, the most commonly encountered mechanism of resistance involves the target enzymes of the azoles, which are responsible for the biosynthesis of ergosterol. Point mutations in the gene (ERG11) encoding for the target enzyme lead to an altered target with decreased affinity for azoles. Overexpression of ERG11 results in the production of high concentrations of the target enzyme, creating the need for higher intracellular drug concentrations to inhibit all of the enzyme molecules in the cell.
The second major mechanism of drug resistance involves active efflux of fluconazole out of the cell through the activation of two types of multidrug efflux transporters; the major facilitators (encoded by MDR genes) and those of the ATP-binding cassette superfamily (encoded by CDR genes). Upregulation of the MDR gene leads to fluconazole resistance, where as, upregulation of CDR genes may lead to resistance to multiple azoles.
Resistance in Candida glabrata usually includes upregulation of CDR genes resulting in resistance to multiple azoles. For an isolate where the minimum inhibitory concentration (MIC) is 16 to 32 mg/L, the highest fluconazole dose is recommended.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
Clotrimazole is an antifungal agent with a broad spectrum of activity. In general, the in vitro activity of clotrimazole corresponds to that of tolnaftate, griseofulvin, and pyrrolnitrin against dermatophytes (Trichophyton, Microsporum and Epidermophyton species) and to that of the polyenes, amphotericin B and nystatin, against budding fungi (Candida and Histoplasma species).
In vitro, clotrimazole is fungistatic for most isolates of pathogenic fungi at concentrations of 0.02 to 10 mcg/mL. The drug is fungicidal for many isolates of Trichophyton, Microsporum, Epidermophyton and Candida species at concentration of 0.1 to 2 mcg/mL.
No one-step or multiple-step secondary resistance to clotrimazole has developed during successive passages of C. albicans, C. krusei, C. pseudotropicalis, T. mentagrophytes, T. rubrum, Cryptococcus neoformans, Aspergillus niger, and A. nidulans. Only a few isolates have been designated as having primary resistance to clotrimazole: a single isolate of C. guillermondii, six isolates of C. neoformans, three isolates of Paracoccidioides brasiliensis and two isolates of Blakeslea trispora.
Topical application of clotrimazole has been effective in the treatment of skin infections experimentally induced in the guinea pig with T. mentagrophytes and T. quinckeanum.
16 NON-CLINICAL TOXICOLOGY
CANESORAL® (fluconazole)
Acute Toxicity: Fluconazole had extremely low toxicity when administered orally in single doses to male and female mice and rats; no deaths occurred at doses below 1000 mg/kg in either species. The first clinical signs noted were incoordination and decreased activity and respiration at doses greater than 500 mg/kg in mice, while only decreased activity was seen in rats at this 500 mg/kg dose; at higher doses signs included ataxia, prostration, exophthalmia, ptosis, lacrimation, salivation, urinary incontinence, loss of righting reflex and cyanosis. Some signs appeared from 10 minutes post-dose and most regressed by the second day. The deaths which occurred at doses greater than 1000 mg/kg, were generally within 5 hours post-dose, but occasionally up to 3 days post-dose. Death was sometimes preceded by clonic convulsions. Fluconazole also displayed low toxicity after single intravenous doses. No deaths occurred in male or female mice at 200 mg/kg, in rats at 165 mg/kg, or in dogs at 100 mg/kg. Clinical signs, lasting up to 5 to 7 hours, included ataxia, exophthalmia, decreased activity and decreased respiration. Dogs which received single intravenous doses of 100 mg/kg showed only transient clinical signs (ataxia, decreased spontaneous movement and decreased respiration).
Subacute/Chronic Toxicity: Subacute and chronic toxicity studies were conducted by the oral and intravenous routes in mice, rats, and dogs over one, three, six and twelve months. The dose levels used in the 1-month toxicity studies in mice and dogs (2.5 to 30 mg/kg) revealed target organ toxicity without affecting survival. These doses were maintained for use in the 6 month studies, but reduced slightly for the 12 month study.
In all three species, the liver was found to be the primary target organ for fluconazole toxicity. This was evidenced by an increase in serum transaminase concentrations, increases in relative liver weight, and the appearance of liver vacuolation and fatty deposits in the 3- and 6-month studies. These findings were seen more often in males than in females. The 12-month studies in rats and dogs confirmed the results of the 6 month studies. The magnitude of the hepatic changes in all three species was never severe. In addition, in mice treated for 6 months and rats for 12 months, followed by withdrawal of drug, the changes regressed completely within 3 months. In all three species, high doses of fluconazole raised cytochrome P-450 concentrations and caused proliferation of the smooth endoplasmic reticulum. The increased liver weight observed appeared to be due in part to enzyme induction and adaptive hypertrophy.
Two week and six-month parenteral studies were also conducted in mice, rats, and dogs. In the mouse and rat studies, similar mild liver changes occurred as seen in the oral studies. In the rat, all the changes regressed within 2 months of drug withdrawal.
Cardiotoxicity: Administration of fluconazole (30mg/kg for 14 days; mean plasma concentrations of 39.9 to 71.9 mcg/ml) to dogs chronically instrumented to record cardiovascular parameters had no effect on cardiac contractility. However, an increase in blood pressure, left ventricular systolic and end-diastolic pressures and the QTc interval of the ECG was observed when compared to vehicle treated animals. These effects were proportional to drug plasma levels.
Carcinogenicity: A 24-month study was conducted in mice at 2.5, 5.0 and 10.0 mg/kg. The highest dose was chosen with reference to hepatic changes observed in the six-month study. Mild hepatic fatty deposition was observed in all dose groups. A few cases of centrilobular hypertrophy were also observed in males at 5 and 10 mg/kg. The only tumors seen were those which occurred spontaneously in the strain of mouse used, and their incidence was not treatment related.
A 24-month study was also done in rats at 2.5, 5.0, and 10 mg/kg. The target organ was again the liver with centrilobular fatty deposition observed in males at all doses. There was a slight, but statistically significant, increase in the incidence of hepatocellular adenomas in male rats with increasing doses of fluconazole. There were no hepatocellular carcinomas in any group. The incidence of the hepatocellular adenomas was also higher than the historical in-house controls. There was also a decreased incidence of mammary gland fibroadenomas in females and benign adrenal medullary phaeochromocytomas in males. Both these decreases were statistically significant.
Fluconazole, when administered to rodents at high dose levels, is known to affect the biochemical balance of male and female hormones. It has been shown to reduce the levels of several steroids, including the ovarian production of 17-beta-estradiol in female rats, increase placental weights, reduce uterine weights, and increase testicular weights in rats in chronic studies. The change in the pattern of tumors in this chronic study of fluconazole in rats is an expected consequence of such a hormone imbalance.
Mutagenicity: Ames testing was done with four different strains of Salmonella with and without metabolic activation. Point mutation activity was assessed in the mouse lymphoma L5178Y system with and without metabolic activation. Urine from mice treated orally with fluconazole was also examined for excreted mutagens. Cytogenetic assays in vivo were conducted in the mouse bone marrow after single doses up to 600 mg/kg and subacute doses of 80 mg/kg for 5 days. Studies in vitro used human lymphocytes with drug concentrations of up to 1000 mcg/mL. Fluconazole revealed no potential mutagenic activity in any of the assays done.
Reproduction and Teratology:
General Fertility (Segments I and III) in rats:
Male rats were treated for 80 days prior to and during mating while female rats were treated for 14 days prior to and during pregnancy and lactation. Both sexes were treated orally with 5, 10, or 20 mg/kg of fluconazole. The treatment was without effect on male or female fertility and labor, and did not impair the development, behavior or fertility of the offspring. The fetuses from the dams sacrificed on day 20 p.i. showed delays in development (an increased incidence of supernumerary ribs at all dose levels and of hydroureters at 20 mg/kg). In the dams allowed to litter, the duration of gestation while remaining within the in-house historical control range, showed a trend towards prolongation in the high dose group. There were no effects on the development, behavior or fertility of the offspring.
Teratology studies (Segment II) in rats:
The results of teratology studies conducted in 4 different laboratories were remarkably consistent.
In one study, dams were treated orally from day 6 to day 15 of gestation with fluconazole at doses of 5, 10, and 20 mg/kg. At these dose levels, there was no evidence of maternal toxicity, embryotoxicity or teratogenicity.
In a second study, the dams were treated orally from day 7 to 17 of gestation with 5, 25, or 125 mg/kg. Placental weights were increased at 25 and 125 mg/kg and three cases of adactyly (a rare malformation in this strain) were observed at the high dose. There was also an increased incidence of fetal anatomical variants: dilatation of the renal pelvis and bending of the ureter at the high dose, and an increased incidence of supernumerary ribs at both mild and high dose levels.
In a third study, dams were treated orally from day 6 to day 15 of gestation at dose levels of 25, 50, 100, or 250 mg/kg. Placental weights were increased at 50 mg/kg and higher doses. At 100 or 250 mg/kg there was increased embryo mortality and a variety of fetal abnormalities such as: reduced or retarded ossification of sternebral elements, postural defects such as wavy ribs, and abnormal cranial ossification. The incidence of supernumerary ribs was increased at all dose levels.
In another study, fluconazole was given orally on days 5-15 of gestation at dose levels of 80, 160, and 320 mg/kg. The vehicle used (Polyethylene Glycol, PEG-400) differed from the vehicle used in earlier studies with fluconazole. It caused maternal effects (an impairment of body weight and food consumption) in all dose groups, with a further drug-related effect being superimposed at the higher dose level. Fluconazole, at all dose levels, resulted in an increased number of dead fetuses and resorption sites and a decreased birthweight of pups. At 320 mg/kg, maternal toxicity was evidenced by decreased food consumption and a reduced increase in body weight. At all dose levels, teratogenicity was evidenced by the presence of multiple visceral and skeletal malformations. Macroglossia, brachygnathia and cleft palate were the main major malformations which showed an increased incidence following dosing with fluconazole. Brachygnathia and cleft palate were increased at doses of 160 and 320 mg/kg while the increase in macroglossia was apparent from 80 mg/kg onwards. Other less commonly observed malformations at 320 mg/kg were those of the eyelids (ablepharia) and ears (bifid ear). A very high incidence of rudimentary 14th ribs, indicating an interference with fetal growth, was observed at all dose levels of fluconazole.
Teratology studies (Segment II) in rabbits:
When dams were treated orally from day 6 to 18 of gestation with 5, 10, or 20 mg/kg of fluconazole, the only treatment-related effect was impaired maternal weight gain at the mid and high dose levels. There was no evidence of fetotoxicity or teratogenicity. At dose levels of 25 and 75 mg/kg, maternal body weights were reduced and placental weights were increased at 75 mg/kg. The top dose was toxic for the dams with 6/8 failing to maintain pregnancy to term. There were no effects on the fetuses at 5 or 25 mg/kg and there were too few fetuses at 75 mg/kg to permit a valid assessment of any drug effect.
Summary of the teratology studies
Fluconazole did not cause fetal malformations at doses of up to 25 mg/kg in rabbits or 50 mg/kg in rats, doses at which maternal toxicity or hormonal disturbances occurred. The fetal effects at higher dose levels and the effects on parturition at doses of 10 mg/kg and above are consistent with the estrogen-lowering properties demonstrated for fluconazole in rats.
Peri- and post-natal study (Segment III) in rats:
Dams were treated intravenously from day 17 of gestation to day 21 post-partum with 5, 20, or 40 mg/kg. This parenteral study confirmed the trend noted in the Segment I study of a delay in the onset of parturition. These disturbances of parturition were reflected in an increase in the number of litters with still-born pups and a slight decrease in pup survival at day 4 in the middle and high dose groups.
Special Toxicology Studies:
- i. Blood compatibility - The formulation of fluconazole dissolved in saline did not cause any hemolysis, flocculation, precipitation or coagulation in human plasma. It did not affect platelet aggregation.
- ii. Ototoxicity in rats - Fluconazole was administered orally to female rats at 100 or 400 mg/kg for 28 days. No ototoxic effect was observed in the Preyer pinna reflex test at 11 different frequencies and no histopathological effect was observed on the cochlea.
- iii. Interaction with AZT - Fluconazole was administered orally to rats at 20 mg/kg twice daily, concurrently with AZT at 40 mg/kg twice daily for 5 days. The combination caused a slight rise in serum sorbitol dehydrogenase as the only treatment-related finding.
Other Studies
Effects on Estrogen Synthesis:
Pregnant rats were treated daily, orally during days 6-15 of gestation with fluconazole (20 or 125 mg/kg) or ketoconazole (10 or 40 mg/kg). Blood samples were taken 3 and 24 hours after the final dose and assayed for 17-beta-estradiol and progesterone. The results show that both fluconazole and ketoconazole affected steroid metabolism. Fluconazole produced a lower estradiol level at both doses at 3 hours but only at the higher dose at 24 hours. Ketoconazole lowered estradiol levels at both doses at 3 hours only. Fluconazole, on the other hand, lowered progesterone levels only at the higher dose at 24 hours, while ketoconazole lowered it at both time points at both doses.
In vitro inhibition of estradiol synthesis was also measured in a broken cell preparation of pregnant rat ovary. The IC50 for inhibition was 0.55 µM for ketoconazole and 8-10 µM for fluconazole. Thus, fluconazole is a much weaker inhibitor of estradiol synthesis.
Effects on Host Defence Mechanisms in Vitro
Fluconazole at concentrations of 5, 10 and 20 mcg/mL, had little effect (3.4, 5.6 and 1.9% inhibition, respectively) on the destruction of [3H]-uridine-labelled Candida albicans blastospores by human polymorphonuclear leukocytes (PMNL) in vitro. This suggests that fluconazole has little or no influence on the mechanisms involved in microbial killing by PMNL. In contrast, ketoconazole at 10 and 20 mcg/mL, significantly reduced (20.9 and 55.9%) the release of [3H]-uridine which indicated that it can suppress the destruction of C. albicans blastospores by human PMNL in vitro.
Similarly, at concentrations of 0.25 to 8 mcg/mL, fluconazole had little effect on the proliferation of concanavalin A and Lipopolysaccharide-stimulated mouse spleen lymphocytes as measured by the uptake of [3H]-thymidine. In contrast, ketoconazole at concentrations up to and including 8 mcg/mL, significantly reduced the uptake of [3H]-thymidine in the presence of both mitogens.
Effects on Key Endocrine Organs
Fluconazole even at the highest concentration (10 mcg/mL) used slightly reduced basal and human chorionic gonadotrophin (hCG)-stimulated testosterone secretion by rat Leydig cells in vitro (27 and 11% inhibition respectively) as compared to ketoconazole which markedly reduced (>50%) both secretions.
The release of corticosterone by suspensions of rat adrenal cells incubated in vitro with ACTH was not inhibited by fluconazole (25 µM) but was inhibited by ketoconazole (1 µM and above). Similarly, fluconazole at the highest concentration (100 µM) used produced modest (approximately 23%)
inhibition of rat adrenal mitochondrial 11-beta-hydroxylase activity in vitro as compared with the marked, concentration-dependent inhibition produced with ketoconazole (3 and 10 µM).
Comparison of the effects of fluconazole and ketoconazole on the production of estrogen in vitro by rat ovarian microsomes showed that fluconazole was approximately 20-fold less potent than ketoconazole as an inhibitor of rat ovarian aromatase (IC50 values 1.4 µM and 29.6 µM respectively).
Thus, fluconazole appears to be relatively free from effects on mammalian steroid synthesis and to be unlikely to give rise to the endocrine-related side effects in man or to inhibit adrenal steroid metabolism in vivo.
CANESTEN® EXTRA STRENGTH EXTERNAL ANTIFUNGAL CREAM (clotrimazole)
General Toxicology:
Non-clinical data reveal no special hazards for humans based on conventional studies of safety pharmacology, genotoxicity, carcinogenic potential and toxicity to reproduction and development. Effects in nonclinical studies, such as the effects on the liver (elevation of transaminases and alkaline phosphatase, liver cell hypertrophy) in the repeat-dose toxicity studies, the effects on the survival of the neonate in a rat fertility study, the species-specific indirect effects on the growth/survival of the fetus in a rat teratology study were observed with oral administration but only at exposures in excess of the maximum human exposure indicating little relevance to clinical use. Given the limited absorption of clotrimazole following a topic application, the potential for toxicity with the occasional use of Canesten 2% cream is further limited.
Carcinogenicity:
Carcinogenicity of clotrimazole was evaluated in a 78-week oral dosing study in rats and the results did not show any carcinogenic effect of clotrimazole.
Genotoxicity:
Clotrimazole has been extensively studied in in vitro and in vivo mutagenicity assays, and no evidence of genotoxic potential was found. In an Ames test, an in vitro biological assay to detect the mutagenicity of chemical compounds, clotrimazole showed no evidence of mutagenic activity. Clotrimazole was found to be non-mutagenic in two additional in vitro studies, a gene mutation test in V79 cell lines and an Unscheduled DNA Synthesis (UDS) in primary rat hepatocytes. Studies evaluating the mutagenicity of clotrimazole in germ cells did not demonstrate mutagenic effects in a spermatogonia test in male hamsters, or in a dominant lethal test in male mice. Additionally, in mice, clotrimazole was not clastogenic in a micronucleus test.
Reproductive and Developmental Toxicology:
At dosages up to 100 mg/kg (oral), clotrimazole was well tolerated by pregnant mice, rats and rabbits, and it had no embryotoxic or teratogenic effect.
When given to pregnant rats at oral doses of 100 mg/kg from day 6 through day 15 of gestation, the number of resorptions was higher and the fetal weights were lower than the controls, but the number of fetal malformations did not differ significantly from that of the control group.
Rats treated with clotrimazole for 10 weeks at dosage up to 50 mg/kg/day did not show any difference from the control group in the duration of estrus, fertility, duration of pregnancy, or in the number of implantations and resorptions. The dose of 50 mg/kg/day impaired the development of the young, and dams receiving this dose level raised fewer offspring.
The intravaginal administration of 100 mg/kg clotrimazole from the sixth to the fifteenth day of gestation was well tolerated by pregnant rats, and there were no harmful effects on the fertilization rate, the resorption rate, the mean fetal weight, and the frequency of stunted forms and of fetuses with slight bone alterations. No malformations were produced by this dose.
Special Toxicology:
Acute Toxicity (Animal)
| Species | LD50 mg/kg |
|---|---|
| Mouse | 761-923 |
| Rat | 708-718 |
| Rabbit | >1000 |
| Cat | >1000; vomiting from 100 mg/kg |
| Dog | >2000; vomiting from 100 mg/ kg |
Multidose Local Tolerance (Animal)
- 1. Primary skin irritation (patch test): no detectable reddening on the intact rabbit skin at either 24 or 72 hours with 1% solution or cream of clotrimazole. Very slight erythema formation after 24 hours in the scarified rabbit skin.
- 2. Primary irritation on conjunctival mucosa: clotrimazole solution or cream produced a transient conjunctival irritation in rabbits, consisting in low-grade reddening and a slight increase in secretion. No grossly detectable alterations were present in either the cornea or the iris of any of the treated animals. Both the cream and solution produced a transient, very slight reddening of the conjunctival mucosa. No alterations occurred on the cornea.
- 3. Subacute (up to 13 weeks) dermal tolerance: the application of 1% clotrimazole solution or 1% cream was systemically well tolerated; no edema was seen on the treated skin, although mild erythema was observed sporadically. The animals in all groups with abraded skin manifested a slight healing tendency.
- 4. Subacute (dogs: 14 days; monkeys: 13 weeks) local vaginal tolerance: the repeated application of clotrimazole vaginal tablets showed a satisfactory local and systemic tolerance. There were no detectable adverse effects, and the cytological examination in monkeys indicated variations consistent with normal estrus cycles.
- 5. Subacute (5 dogs: 30 days; 4 monkeys: 13 weeks; 10 healthy human volunteers: 28 days) local vaginal tolerance. The repeated application of Vaginal Cream showed a satisfactory local and systemic tolerance without adverse effects or abnormalities in vaginal cytology in all species.
Human
In 453 cases under treatment which were evaluated with respect to photosensitivity and phototoxicity, no reactions were encountered.
Twenty normal subjects were tested in a controlled study for sensitivity to ultraviolet radiation. Areas of skin treated with clotrimazole were irradiated for 30 seconds on the first day, and for one-half minute longer each time on every second day thereafter. One of the 20 subjects was irradiated once only; 9 subjects three times, and 10 subjects four times. One subject developed papule formation after the first exposure to ultraviolet radiation.
The topical tolerance of CANESTEN® Vaginal Tablets was studied in 462 patients with Candida or Trichomonas infections of the vagina. Five patients reported irritation (itching and burning after insertion) not necessitating the treatment to be discontinued.
There were undesirable effects in three (0.5%) of 653 patients treated with CANESTEN® Vaginal Cream which were possibly related to treatment. Discontinuation of treatment was necessary in a patient with a sensation of vaginal burning and in another patient with a possible allergic reaction, manifested by vaginal burning, local irritation and erythema. Treatment was, however, continued in a patient with intercurrent cystitis.