


Product Monograph - Jamp Itraconazole Oral Solution
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 02/2024 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed. RECENT MAJOR LABEL CHANGES ................................................................................................................................................ 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS .............................................................................................................. 4
1.1 Pediatrics ........................................................................................................ 4
1.2 Geriatrics ........................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ........................................................... 6
4 DOSAGE AND ADMINISTRATION ................................................................................ 6
4.1 Dosing Considerations .................................................................................... 6
4.2 Recommended Dose and Dosage Adjustment ............................................... 7
4.4 Administration................................................................................................ 7
5 OVERDOSAGE ............................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 8
7 WARNINGS AND PRECAUTIONS ................................................................................. 8
7.1 Special Populations ...................................................................................... 12
7.1.1 Pregnant Women ......................................................................................... 12
7.1.2 Breast-feeding .............................................................................................. 13
7.1.3 Pediatrics ...................................................................................................... 13
7.1.4 Geriatrics ...................................................................................................... 13
8 ADVERSE REACTIONS ............................................................................................... 13
8.1 Adverse Reaction Overview .......................................................................... 13
8.2 Clinical Trial Adverse Reactions .................................................................... 13
8.5 Post-Market Adverse Reactions ................................................................... 14
9 DRUG INTERACTIONS ............................................................................................... 15
9.1 Serious Drug Interactions ............................................................................. 15
9.2 Drug Interactions Overview .......................................................................... 16
9.4 Drug-Drug Interactions ................................................................................. 17
9.5 Drug-Food Interactions ................................................................................ 34
9.6 Drug-Herb Interactions ................................................................................. 34
9.7 Drug-Laboratory Test Interactions ............................................................... 34
10 CLINICAL PHARMACOLOGY ...................................................................................... 34
10.1 Mechanism of Action ................................................................................... 35
10.2 Pharmacodynamics Human Pharmacodynamics .......................................... 35
10.3 Pharmacokinetics ......................................................................................... 36
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 41
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 41
PART II: SCIENTIFIC INFORMATION ...................................................................................... 42
13 PHARMACEUTICAL INFORMATION ........................................................................... 42
14 CLINICAL TRIALS ....................................................................................................... 43
14.1 Clinical Trials by Indication ........................................................................... 43
Oropharyngeal Candidiasis ........................................................................................... 43
Esophageal Candidiasis................................................................................................. 44
Oral and/or Esophageal Candidiasis ............................................................................. 45
15 MICROBIOLOGY ........................................................................................................ 45
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 47
17 SUPPORTING PRODUCT MONOGRAPHS ....................................................................... 53
PATIENT MEDICATION INFORMATION ................................................................................. 54
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Itraconazole Oral Solution (itraconazole) 10 mg/mL is indicated for:
- the treatment of oral and/or esophageal candidiasis in adult HIV-positive or other immunocompromised patients.
Itraconazole oral solution as treatment for oral and/or esophageal candidiasis was not investigated in neutropenic patients. Due to the pharmacokinetic properties (see 10.3 Pharmacokinetics), JAMP Itraconazole Oral Solution is not recommended for initiation of treatment in patients at immediate risk of systemic candidiasis.
Note: Itraconazole oral solution and itraconazole capsules should not be used interchangeably.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of itraconazole oral solution in pediatric patients has not been established; therefore Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics).
1.2 Geriatrics
Geriatrics (>65 years of age): Clinical data on the use of itraconazole oral solution in elderly patients are limited. It is advised to use itraconazole oral solution in these patients only if it is determined that the potential benefit outweighs the potential risks (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
- JAMP Itraconazole Oral Solution should not be administered to patients with evidence of ventricular dysfunction, such as congestive heart failure (CHF) or a history of CHF except for the treatment of life-threatening or other serious infections (see Table 1, Calcium Channel Blockers; 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Use in Patients with Underlying Cardiac Disease and 8.5 Post-Market Adverse Reactions).
- Coadministration with JAMP Itraconazole Oral Solution, a potent cytochrome P450 3A4 isoenzyme system (CYP3A4) inhibitor, causes elevated plasma concentrations of drugs metabolized by this pathway which may increase or prolong both therapeutic and adverse effects to such an extent that a potentially serious situation may occur. Drugs that are contraindicated in combination with itraconazole are listed in Table 1 (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX and 9.4 Drug-Drug Interactions, Table 4).
Table 1: Drugs that are contraindicated with JAMP Itraconazole Oral Solution
| Drug Class | Drugs within Class that are Contraindicated with JAMP Itraconazole Oral Solution |
|---|---|
| Analgesics | methadone |
| Antiarrhythmics | disopyramide, dronedarone, quinidine |
| Anticoagulants and Antiplatelet Drugs | ticagrelor, apixaban, rivaroxaban |
| Antifungals | isavuconazole |
| Antimigraine Drugs | ergot alkaloids, such as dihydroergotamine, ergometrine (ergonovine), ergotamine, eletriptan |
| Antineoplastics | irinotecan, venetoclax (for chronic lymphocytic leukemia/small lymphocytic lymphoma patients during initiation/titration/ramp-up phase). |
| Antipsychotics, Anxiolytics and Hypnotics | lurasidone, pimozide, triazolam |
| Antivirals | asunaprevir (boosted) |
| Calcium Channel Blockers | felodipine |
| Cardiovascular Drugs | ivabradine, ranolazine |
| Diuretics | eplerenone |
| Gastrointestinal Drugs | domperidone, naloxegol |
| Lipid Regulating Drugs | lomitapide, lovastatin, simvastatin |
| Urologic Drugs | fesoterodine, in subjects with moderate to severe renal impairment, or moderate to severe hepatic impairment solifenacin, in subjects with severe renal impairment or moderate to severe hepatic impairment. |
| Miscellaneous Drugs and Other Substances | colchicine, in subjects with renal or hepatic impairment, eliglustat. |
- JAMP Itraconazole Oral Solution is contraindicated in patients with a known hypersensitivity to itraconazole or its excipients. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- There is limited information regarding cross-hypersensitivity between itraconazole and other azole antifungal agents. Caution should be used in prescribing JAMP Itraconazole Oral Solution to patients with hypersensitivity to other azoles.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
When JAMP Itraconazole Oral Solution may be indicated, the type of organism responsible for the infection should be isolated and identified; however, therapy may be initiated prior to obtaining these results, when clinically warranted.
For optimal absorption, itraconazole oral solution should be taken without food (patients are advised to refrain from eating for at least 1 hour after intake).
4.2 Recommended Dose and Dosage Adjustment
Oral Candidiasis: The recommended dosage of itraconazole oral solution for oral candidiasis is 200 mg (20 mL of oral solution) daily in a single dose or divided doses; treatment should continue for 1-2 weeks to decrease the likelihood of relapse.
Esophageal Candidiasis: The recommended dosage for esophageal candidiasis is 100 mg (10 mL of oral solution) daily for a minimum treatment of three weeks. Treatment should continue for two weeks following resolution of symptoms. Doses of up to 200 mg (20 mL of oral solution) per day may be used based on medical assessment of the patient's response to therapy.
Special Populations
Pediatrics (<18 years of age):
Health Canada has not authorized an indication for pediatric use. JAMP Itraconazole Oral Solution should not be used in pediatric patients unless the potential benefit outweighs the potential risks (se 7.1 Special Populations).
Geriatrics (>65 years of age):
Clinical data on the use of itraconazole oral solution in elderly patients are limited. It is advised to use Itraconazole oral solution in these patients only if it is determined that the potential benefit outweighs the potential risks. In general, it is recommended that the dose selection for an elderly patient should be taken into consideration, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Patients with Hepatic Impairment
Limited data are available on the use of oral itraconazole in patients with hepatic impairment. Caution should be exercised when this drug is administered in this patient population (see
7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics,
Special Populations and Conditions, Hepatic Insufficiency).
Patients with Renal Impairment
Limited data are available on the use of oral itraconazole in patients with renal impairment. The exposure of itraconazole may be lower in some patients with renal insufficiency. Caution should be exercised when this drug is administered in this patient population and adjusting the dose may be considered (see 7 WARNINGS AND PRECAUTIONS, Renal; 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
4.4 Administration
The solution should be swished in the oral cavity and swallowed. There should be no rinsing after swallowing.
5 OVERDOSAGE
There is no experience of overdosage with itraconazole oral solution; however, based on animal toxicity data, symptoms of a gastrointestinal or central nervous system nature may be expected to occur.
Although no data are available for itraconazole, standard supportive treatment should be applied as necessary.
It has been reported that itraconazole cannot be removed by hemodialysis. No specific antidote is available.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Solution 10 mg/mL | caramel flavour, cherry flavour, hydrochloric acid, hydroxypropyl-ß- cyclodextrin, propylene glycol, purified water, sodium hydroxide, sodium saccharin, and sorbitol. |
JAMP Itraconazole Oral Solution is available as a 10 mg itraconazole per mL solution, with 150 mL in each amber glass bottle.
A dosing cup is supplied with the JAMP Itraconazole Oral Solution. The dosing cup is provided in the JAMP Itraconazole Oral Solution package to accurately measure the amount of solution needed. JAMP Itraconazole Oral Solution should be poured into the end of the cup with the graduations which indicate dosing amounts (2.5 mL, 5 mL, 10 mL, 15 mL and 20 mL). There are arrows on the sides of the dosing cup showing which end to pour the solution into.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
JAMP Itraconazole Oral Solution and Itraconazole capsules should not be used interchangeably. JAMP Itraconazole Oral Solution is indicated only for the treatment of oropharyngeal and/or esophageal candidiasis. The efficacy of itraconazole oral solution for other indications is unknown. The two dosage forms have different absorption profiles (see 10.3
Pharmacokinetics).
In patients receiving continuous treatment of more than one month and in patients developing symptoms such as anorexia, nausea, vomiting, fatigue, abdominal pain or dark urine, it is advisable to monitor liver function. If tests are abnormal, treatment should be terminated.
In systemic candidosis, if fluconazole-resistant strains of Candida species are suspected, it cannot be assumed that these are sensitive to itraconazole, hence it is recommended to have their sensitivity tested before the start of itraconazole therapy (see 15 MICROBIOLOGY, Resistance and Cross-Resistance).
Carcinogenesis and Mutagenesis
JAMP Itraconazole Oral Solution contains the excipient hydroxypropyl-β-cyclodextrin, which produced adenocarcinomas in the large intestine and exocrine pancreas in a rat carcinogenicity study, but not in a similar mouse carcinogenicity study. The clinical relevance of these findings is unknown. See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity for discussion on itraconazole animal data.
Cardiovascular
Cardiac Dysrhythmias
Life-threatening cardiac dysrhythmias and/or sudden death have occurred in patients using drugs such as methadone, pimozide or quinidine concomitantly with itraconazole and/or other CYP3A4 inhibitors. Concomitant administration of these drugs with itraconazole is contraindicated (see 2 CONTRAINDICATIONS, 9.1 Serious Drug Interactions and 9.4 Drug- Drug Interactions, Table 4).
Use in Patients with Underlying Cardiac Disease
Itraconazole has been associated with reports of CHF. In post-marketing experience, heart failure was more frequently reported in patients receiving a total daily dose of 400 mg than among those receiving lower total daily doses. This suggests that the risk of heart failure might increase with the total daily dose of itraconazole.
JAMP Itraconazole Oral Solution should not be used in patients with evidence of ventricular dysfunction such as CHF or a history of CHF unless the benefit clearly outweighs the risk.
The benefit/risk assessment should take into consideration factors such as the severity of the indication, the dosing regimen (e.g., total daily dose), and the individual risk factors for congestive heart failure. These risk factors include cardiac disease, such as ischemic and valvular disease; significant pulmonary disease, such as chronic obstructive pulmonary disease; renal failure and other edematous disorders. Such patients should be informed of the signs and symptoms of congestive heart failure, treated with caution, and monitored for signs and symptoms of congestive heart failure during treatment; if such signs or symptoms do occur during treatment, JAMP Itraconazole Oral Solution should be discontinued (see 8.5 Post-Market Adverse Reactions and 9 DRUG INTERACTIONS).
Itraconazole has been shown to have a negative inotropic effect. When itraconazole was administered intravenously to anesthetized dogs, a dose-related negative inotropic effect was documented. In a healthy volunteer study (n=8) of itraconazole for injection, a transient asymptomatic decrease of the left ventricular ejection fraction was observed using gated SPECT imaging; this resolved before the next infusion, 12 hours later.
Calcium channel blockers can have negative inotropic effects which may be additive to those of itraconazole. In addition, itraconazole can inhibit the metabolism of calcium channel blockers.
Therefore, caution should be used when coadministering itraconazole and calcium channel blockers due to an increased risk of CHF. Concomitant administration of JAMP Itraconazole Oral Solution with felodipine is contraindicated.
Cases of CHF, peripheral edema, and pulmonary edema have been reported in the post- marketing period among patients being treated for onychomycosis and/or systemic fungal infections (see 8.5 Post-Market Adverse Reactions).
Driving and Operating Machinery
Adverse reactions such as dizziness, visual disturbances and hearing loss have been reported while taking itraconazole. These adverse reactions may impair the ability to drive a vehicle and operate machinery (see 8.5 Post-Market Adverse Reactions).
Ear/Nose/Throat
Hearing Loss
Transient or permanent hearing loss has been reported in patients receiving treatment with itraconazole. Several of these reports included concurrent administration of quinidine, which is contraindicated (see 2 CONTRAINDICATIONS). The hearing loss usually resolves when treatment is stopped but can persist in some patients.
Hepatic/Biliary/Pancreatic
Rare cases of serious hepatotoxicity (including liver failure and death) have been observed with itraconazole treatment. Some of these cases had neither pre-existing liver disease nor a serious underlying medical condition and some of these cases developed within the first week of treatment.
In patients with elevated or abnormal liver enzymes or active liver disease, or who have experienced liver toxicity with other drugs, treatment with itraconazole oral solution is strongly discouraged unless there is a serious or life-threatening situation where the expected benefit exceeds the risk. Liver function monitoring should be done in patients with pre-existing hepatic function abnormalities or those who have experienced liver toxicity with other medications and should be considered in all patients receiving itraconazole oral solution.
Treatment should be stopped immediately, and liver function testing should be conducted in patients who develop signs and symptoms suggestive of liver dysfunction. Such signs and symptoms include unusual fatigue, anorexia, nausea and/or vomiting, jaundice, abdominal pain, dark urine or pale stools (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX; 7 WARNINGS AND PRECAUTIONS, General, and 8.5 Post-Market Adverse Reactions). Itraconazole binds extensively to plasma proteins.
Use in Patients with Hepatic Insufficiency
Limited data are available on the use of oral itraconazole in patients with hepatic impairment. Caution should be exercised when the drug is administered in this patient population. It is recommended that patients with impaired hepatic function be carefully monitored when taking itraconazole. In a clinical trial in cirrhotic patients, the mean terminal half-life of itraconazole was increased by 131% and its mean Cmax decreased by 47%. It is recommended that the prolonged elimination half-life of itraconazole observed in the single oral dose clinical trial with itraconazole capsules in cirrhotic patients be considered when deciding to initiate therapy with other medications metabolized by CYP3A4 (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Immune
Use in Acquired Immunodeficiency Syndrome (AIDS) and Neutropenic Patients
Studies with itraconazole capsules in neutropenic and AIDS patients have indicated that itraconazole plasma concentrations are lower than those in healthy subjects (particularly in those patients who are achlorhydric). However, the bioavailability of itraconazole oral solution, when tested in AIDS patients, was found satisfactory and not altered by the stage of HIV infection.
The results from a study in which 8 HIV-infected individuals were treated with zidovudine, 8 ± 0.4 mg/kg/day with or without itraconazole capsules 100 mg b.i.d., showed that the pharmacokinetics of zidovudine were not affected during concomitant administration of itraconazole capsules.
Monitoring and Laboratory Tests
Due to the presence of an active metabolite, hydroxy-itraconazole, plasma levels monitored by bioassay will yield plasma levels roughly three times higher than that obtained by high-pressure liquid chromatography (HPLC), unless solvent conditions for the HPLC assay are adjusted to allow simultaneous detection of both the parent drug and the metabolite.
Liver function monitoring should be done in patients with pre-existing hepatic abnormalities, or those who have experienced liver toxicity with other medications and should also be considered in all patients receiving treatment with itraconazole oral solution.
Hypokalemia has been reported in a few patients. Therefore, serum potassium should be monitored in patients at risk during high-dose itraconazole therapy.
Neurologic
If neuropathy occurs that may be attributable to itraconazole oral solution, the treatment should be discontinued.
Renal
Use in Patients with Renal Insufficiency
Limited data are available on the use of oral itraconazole in patients with renal impairment. The exposure of itraconazole may be lower in some patients with renal insufficiency. Caution should be exercised when this drug is administered in this patient population and adjusting the dose may be considered (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
In a few patients, hypokalemia has been reported. Consequently, serum potassium should be monitored in patients at risk during high-dose itraconazole therapy.
Itraconazole cannot be removed by hemodialysis.
Respiratory
Cystic Fibrosis
In cystic fibrosis patients, variability in therapeutic levels of itraconazole was observed with steady-state dosing of itraconazole oral solution using 2.5 mg/kg b.i.d. Steady-state concentrations of >250 ng/mL were achieved in approximately 50% of subjects greater than 16 years of age, but in none of the patients less than 16 years of age. If a patient does not respond to itraconazole oral solution, consideration should be given to switching to alternative therapy.
7.1 Special Populations
7.1.1 Pregnant Women
JAMP Itraconazole Oral Solution must not be used during pregnancy except for life-threatening cases where the potential benefit to the mother outweighs the potential harm to the fetus. Itraconazole has been shown to produce teratogenic effects (major skeletal and secondary soft tissue defects) when administered at high doses (40 mg/kg/day, 5 times the maximum recommended human dose (MRHD) or higher) to pregnant rats. When administered to pregnant mice at high doses (80 mg/kg/day, 10 times MRHD or higher), itraconazole has been shown to produce encephaloceles and/or macroglossia.
There is limited information on the use of itraconazole during pregnancy. During post-marketing experience, cases of congenital abnormalities have been reported. These cases included skeletal, genitourinary tract, cardiovascular and ophthalmic malformations, as well as chromosomal and multiple malformations. A causal relationship with itraconazole oral solution has not been established.
Pregnancy should be avoided in women using itraconazole and for 2 months following end of treatment. In women of childbearing potential, a reliable method of barrier contraception must always be used in combination with other methods of contraception e.g. oral or other hormonal contraceptives (see 9 DRUG INTERACTIONS).
7.1.2 Breast-feeding
Itraconazole is excreted in human milk; therefore, the patient should be advised to discontinue nursing while taking JAMP Itraconazole Oral Solution.
7.1.3 Pediatrics
Pediatrics (<18 years of age): The efficacy and safety of itraconazole oral solution have not been established in pediatric patients. JAMP Itraconazole Oral Solution should not be used in pediatric patients unless the potential benefit outweighs the potential risks. Clinical data on the use of itraconazole oral solution in pediatric patients are limited. A pharmacokinetic study was conducted with itraconazole oral solution in 26 pediatric patients, ages 6 months to 12 years, requiring systemic antifungal treatment. Itraconazole was dosed at 5 mg/kg once daily for 2 weeks and no serious unexpected adverse events were reported (see 10.3 Pharmacokinetics).
Toxicological studies have shown that itraconazole, when administered to rats, can produce bone toxicity. While no such toxicity has been reported in adult patients, the long-term effect of itraconazole in children is unknown (see 16 NON-CLINICAL TOXICOLOGY).
7.1.4 Geriatrics
Geriatrics (>65 years of age): Clinical data on the use of itraconazole oral solution in elderly patients are limited. It is advised to use itraconazole oral solution in these patients only if it is determined that the potential benefit outweighs the potential risks. In general, it is recommended that the dose selection for an elderly patient should be taken into consideration, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Itraconazole has been associated with rare cases of serious hepatotoxicity, including liver failure and death. Some of these cases had neither pre-existing liver disease nor a serious underlying medical condition. If clinical signs or symptoms develop that are consistent with liver disease, treatment should be discontinued, and liver function testing performed. Before consideration is given to reinstituting therapy, the risks and benefits of itraconazole use should be reassessed (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Itraconazole oral solution
The adverse event profile was analyzed for 889 HIV-positive and other immunocompromised patients receiving itraconazole oral solution for the treatment of oral and esophageal candidiasis. The most frequently reported adverse events were of gastrointestinal origin. The total observed incidence of adverse events that are possibly or directly drug related, during treatment or within 14 days post-treatment for itraconazole oral solution is 18.2%. A listing of adverse events reported with a frequency ≥1% for itraconazole in all worldwide studies of oropharyngeal and esophageal candidiasis is presented in Table 3.
Table 3: Adverse experience incidence ≥1.0% in worldwide trials of oropharyngeal and esophageal candidiasis, by body system
| Body System/adverse event | itraconazole n=889 |
|---|---|
Gastrointestinal system disorder Nausea Diarrhea Vomiting Abdominal pain | 12.3% 5.3% 4.5% 3.4% 2.5% |
| Skin and appendages disorders Rash | 2.4% 1.3% |
| Central and peripheral nervous system Headache | 1.7% 1.1% |
| Liver and biliary system disorders | 1.3% |
Special senses Taste perversion | 1.1% 1.0% |
| Body as a whole | 1.0% |
8.5 Post-Market Adverse Reactions
Worldwide post-marketing experiences with the use of itraconazole (across all three itraconazole formulations: itraconazole capsules, itraconazole oral solution and itraconazole IV) include the adverse events listed below.
General disorders and administration site conditions: edema, pyrexia, generalized edema, face edema, chest pain, pain, fatigue, chills
Blood and lymphatic system disorders: granulocytopenia, leukopenia, neutropenia, thrombocytopenia
Cardiac disorders: congestive heart failure, cardiac failure, left ventricular failure, tachycardia
Ear and labyrinth disorders: tinnitus, transient or permanent hearing loss
Endocrine disorders: Pseudoaldosteronism
Eye disorders: visual disturbances, including vision blurred and diplopia
Gastrointestinal disorders: pancreatitis, abdominal pain, vomiting, dyspepsia, nausea, diarrhea, constipation, dysgeusia, gastrointestinal disorder, flatulence
Hepatobiliary disorders: serious hepatotoxicity (including some cases of fatal acute liver failure), hepatitis, reversible increases in hepatic enzymes, hepatic function abnormal, hepatic failure, hyperbilirubinemia, jaundice
Immune system disorders: serum sickness, angioneurotic edema, anaphylactic, anaphylactoid and allergic reactions, hypersensitivity
Infections and Infestations: sinusitis, upper respiratory tract infection, rhinitis
Investigations: blood creatine phosphokinase increased, alanine aminotransferase increased, aspartate aminotransferase increased, blood alkaline phosphatase increased, blood lactate dehydrogenase increased, blood urea increased, gamma-glutamyltransferase increased, hepatic enzyme increased, urine analysis abnormal
Metabolism and nutrition disorders: hyperglycemia, hypertriglyceridemia, hypokalemia, hypomagnesemia
Musculoskeletal and connective tissue disorders: myalgia, arthralgia
Nervous system disorders: peripheral neuropathy, paresthesia, hypoesthesia, headache, dizziness, somnolence, tremor
Psychiatric disorders: confusional state
Renal and urinary disorders: pollakiuria, urinary incontinence, renal impairment
Reproductive system and breast disorders: menstrual disorders, erectile dysfunction Respiratory, thoracic and mediastinal disorders: pulmonary edema, dyspnea, dysphonia
Skin and subcutaneous tissue disorders: toxic epidermal necrolysis, Stevens-Johnson syndrome, acute generalized exanthematous pustulosis, erythema multiforme, exfoliative dermatitis, leukocytoclastic vasculitis, urticaria, alopecia, photosensitivity, rash, pruritus, rash erythematous, hyperhidrosis
Vascular disorders: hypertension, hypotension
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
| Serious Drug Interactions |
|---|
|
9.2 Drug Interactions Overview
Itraconazole is a drug with a high interaction potential. The various types of interaction and associated general recommendations are described below. In addition, Table 4 provides listing examples of drugs that may interact with itraconazole, organized per drug family for easy reference.
Itraconazole is mainly metabolized through CYP3A4. Other substances that either share this metabolic pathway or modify CYP3A4 activity may influence the pharmacokinetics of itraconazole. Coadministration of itraconazole with moderate or potent CYP3A4 inducers may decrease the bioavailability of itraconazole and hydroxy-itraconazole to such an extent that efficacy may be reduced. Coadministration with moderate or potent inhibitors of CYP3A4 may increase the bioavailability of itraconazole, which may result in increased or prolonged pharmacologic effects of itraconazole.
Itraconazole and its major metabolite, hydroxy-itraconazole are potent CYP3A4 inhibitors. Itraconazole is an inhibitor of the drug transporters P-glycoprotein and breast cancer resistance protein (BCRP). Itraconazole can inhibit the metabolism of drugs metabolized by CYP3A4 and can inhibit the drug transport by P-glycoprotein and/or BCRP, which may result in increased plasma concentrations of these drugs and/or their active metabolite(s) when they are administered with itraconazole. These elevated plasma concentrations may increase or prolong both therapeutic and adverse effects of these drugs. For some drugs, coadministration with itraconazole may result in decreased plasma concentrations of the drug or of the active moiety of the drug. This may result in reduced efficacy of the drug.
Following cessation of medical treatment with itraconazole, plasma concentrations decrease below the detection limit within 7 to 14 days, depending on the dose and duration of treatment. In patients with hepatic cirrhosis or in subjects receiving CYP3A4 inhibitors the plasma concentrations decline slower. This is particularly important for consideration when initiating therapy with drugs whose metabolism is affected by itraconazole.
The following general recommendations apply, unless stated differently in Table 4.
CONTRAINDICATED: Under no circumstances is the drug to be coadministered with itraconazole. This applies to:
- CYP3A4 substrates for which increased plasma concentrations may increase or prolong therapeutic and/or adverse effects to such an extent that a potentially serious situation may occur (see 2 CONTRAINDICATIONS).
NOT RECOMMENDED: It is recommended that the use of the drug be avoided, unless the benefits outweigh the potentially increased risks. If coadministration cannot be avoided, clinical monitoring is recommended, and the dosage of itraconazole and/or the coadministered drug adapted as deemed necessary. When appropriate, it is recommended that plasma concentrations be measured. This applies to:
- Moderate or potent CYP3A4 inducers: not recommended from 2 weeks before and during treatment with itraconazole
- CYP3A4/P-gp/BCRP substrates for which increased or decreased plasma concentrations result in significant risk: not recommended during and up to 2 weeks after treatment with itraconazole.
USE WITH CAUTION: Careful monitoring is recommended when the drug is coadministered with itraconazole. Upon coadministration, it is recommended that patients be monitored closely and the dosage of itraconazole and/or the coadministered drug adapted as deemed necessary. When appropriate, it is recommended that plasma concentrations be measured. This applies to:
- Moderate or potent inhibitors of CYP3A4
- CYP3A4/P-gp/BCRP substrates for which increased or decreased plasma concentrations result in a clinically relevant risk
The list of examples of interacting drugs in the table below is not comprehensive and therefore the label of each drug that is coadministered with itraconazole should be consulted for information related to the route of metabolism, interaction pathways, potential risks, and specific actions to be taken with regards to coadministration. The drugs listed in this table are based on either drug interaction studies or case reports, or potential interactions based on the mechanism of interaction. This list is not all-inclusive.
9.4 Drug-Drug Interactions
Table 4: Examples of drugs that may interact with itraconazole oral solution
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| Alpha Blockers | ||
Alfuzosin Silodosin Tamsulosin | Alfuzosin Cmax (↑↑), AUC (↑↑)2 Silodosin Cmax (↑↑), AUC (↑↑)2 Tamsulosin Cmax (↑↑), AUC (↑↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of alfuzosin/silodosin/ tamsulosin- related adverse reactions4. |
| Analgesics | ||
Alfentanil Buprenorphine (IV and sublingual) Oxycodone Sufentanil | Alfentanil AUC (↑↑ to ↑↑↑↑)2 Buprenorphine Cmax (↑↑), AUC (↑↑)2 Oxycodone Cmax ↑, AUC ↑↑ Sufentanil conc. increase (extent unknown)2,3 | USE WITH CAUTION, monitor for adverse reactions related to the analgesic4, dose reduction of alfentanil/buprenorphine/ oxycodone/sufentanil may be necessary. |
| Fentanyl | Fentanyl IV AUC (↑↑)2 Fentanyl other form conc. increase (extent unknown)2,3 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of fentanyl-related adverse reactions4. |
| Methadone | (R)-methadone Cmax (↑), AUC (↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of methadone-related adverse reactions, such as potentially life- threatening respiratory depression, QT prolongation and TdP. |
| Anti-arrhythmics | ||
| Digoxin | Digoxin Cmax ↑, AUC ↑ | USE WITH CAUTION, monitor for digoxin adverse reactions, dose reduction of digoxin may be necessary4. |
| Disopyramide | Disopyramide conc. increase (↑↑)2,3 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of disopyramide-related |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| adverse reactions, such as serious arrhythmias including TdP. | ||
| Dronedarone | Dronedarone Cmax (↑↑↑), AUC (↑↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of dronedarone-related adverse reactions, such as QT prolongation and cardiovascular death. |
| Quinidine | Quinidine Cmax ↑, AUC ↑↑ | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of quinidine-related adverse reactions, such as QT prolongation, TdP, hypotension, confusion and delirium. |
| Antibacterials | ||
| Ciprofloxacin Erythromycin | Itraconazole Cmax ↑, AUC ↑ | USE WITH CAUTION, monitor for itraconazole adverse reactions, dose reduction of itraconazole may be necessary. |
| Clarithromycin | Clarithromycin conc. increase (extent unknown)2,3 Itraconazole Cmax ↑, AUC ↑ | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or clarithromycin4, dose reduction of itraconazole and/or clarithromycin may be necessary. |
Isoniazid Rifampicin | Isoniazid: itraconazole conc. (↓↓↓)2,3 Rifampicin: itraconazole AUC ↓↓↓ | NOT RECOMMENDED from 2 weeks before and during treatment with itraconazole, Itraconazole efficacy may be reduced. |
| Rifabutin | Rifabutin conc. increase (extent unknown)2,3 Itraconazole: Cmax ↓↓, AUC ↓↓ | NOT RECOMMENDED from 2 weeks before, during and for 2 weeks after treatment with itraconazole. Itraconazole efficacy may be reduced and increased risk of rifabutin- |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| related adverse reactions4. | ||
| Anticoagulants and Antiplatelet Drugs | ||
| Vorapaxar | Vorapaxar Cmax (↑), AUC (↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of vorapaxar-related adverse reactions4. |
| Edoxaban | Edoxaban Cmax (↑), AUC (↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of edoxaban-related adverse reactions4. If concomitant use cannot be avoided, dose reduction of edoxaban is recommended |
| Coumarins (e.g., warfarin) Cilostazol | Coumarins (e.g., warfarin) conc. increase (extent unknown)2,3 Cilostazol Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for coumarins/cilostazol adverse reactions, dose reduction of coumarins/cilostazol may be necessary4. |
| Dabigatran | Dabigatran Cmax (↑↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for dabigatran adverse reactions, dose reduction of dabigatran may be necessary4. |
| Ticagrelor | Ticagrelor Cmax (↑↑), AUC (↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of ticagrelor-related adverse reactions, such as bleeding. |
Apixaban Rivaroxaban | Apixaban Cmax (↑), AUC (↑)2 Rivaroxaban Cmax (↑), AUC (↑ to ↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of apixaban/rivaroxaban-related adverse reactions4. |
| Anticonvulsants | ||
| Carbamazepine | Carbamazepine conc. (↑)2,3 Itraconazole conc. (↓↓)2,3 | NOT RECOMMENDED from 2 weeks before, during and for 2 |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| weeks after treatment with itraconazole. Itraconazole efficacy may be reduced and increased risk for carbamazepine-related adverse reactions4. | ||
Phenobarbital Phenytoin | Phenobarbital: itraconazole conc. (↓↓↓)2,3 Phenytoin: itraconazole AUC ↓↓↓ | NOT RECOMMENDED from 2 weeks before and during treatment with itraconazole. Itraconazole efficacy may be reduced. |
| Antidiabetics | ||
| Repaglinide Saxagliptin | Repaglinide Cmax ↑, AUC ↑ Saxagliptin Cmax (↑↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for repaglinide/saxagliptin adverse reactions, dose reduction of repaglinide/saxagliptin may be necessary4. |
| Antihelminthics, antifungals and antiprotozoals | ||
| Quinine | Quinine Cmax ↔, AUC ↑ | USE WITH CAUTION, monitor for quinine adverse reactions4. Refer to the Product Monograph (PM) for specific actions to be taken. |
| Isavuconazole | Isavuconazole Cmax (↔), AUC (↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of isavuconazole-related adverse reactions, such as hepatic adverse reactions, hypersensitivity reactions, embryo-fetal toxicity and cardiac disorders, including QTc interval shortening. |
| Praziquantel | Praziquantel Cmax (↑↑), AUC (↑)2 | USE WITH CAUTION, monitor for praziquantel adverse reactions, dose reduction of praziquantel may be necessary4. |
| Antihistamines | ||
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
Bilastine Ebastine Rupatadine | Bilastine Cmax (↑↑), AUC (↑)2 Ebastine Cmax ↑↑, AUC ↑↑↑ Rupatadine conc. increase (↑↑↑↑)2,3 | USE WITH CAUTION, monitor for bilastine/ebastine/rupatadine adverse reactions4, dose reduction of bilastine/ebastine/rupatadine may be necessary. |
| Antimigraine Drugs | ||
| Eletriptan | Eletriptan Cmax (↑↑), AUC (↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Coadministration of eletriptan with Itraconazole can elevate plasma eletriptan concentrations which could result in serious adverse events. |
| Ergot alkaloids (such as dihydroergotamine, ergometrine (ergonovine), ergotamine) | Ergot alkaloids conc. increase (extent unknown)2,3 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of ergot alkaloid-related adverse reactions, such as ergotism. |
| Antineoplastics | ||
Bortezomib Brentuximab vedotin Busulfan Erlotinib Gefitinib Imatinib Ixabepilone Nintedanib Pemigatinib Ponatinib Ruxolitinib Sonidegib Tretinoin (oral) Vandetanib | Bortezomib AUC (↑)2 Brentuximab vedotin AUC (↑)2 Busulfan Cmax ↑, AUC ↑ Erlotinib Cmax (↑↑), AUC (↑)2 Gefitinib Cmax ↑, AUC ↑ Imatinib Cmax (↑), AUC (↑)2 Ixabepilone Cmax (↔), AUC (↑)2 Nintedanib Cmax (↑), AUC (↑)2 Pemigatinib Cmax ↑, AUC ↑ Ponatinib Cmax (↑), AUC (↑)2 Ruxolitinib Cmax (↑), AUC (↑)2 Sonidegib Cmax (↑), AUC (↑↑)2 Tretinoin Cmax (↑), AUC (↑)2 Vandetanib Cmax ↔, AUC ↑ | USE WITH CAUTION, monitor for adverse reactions related to the antineoplastic drug4, dose reduction of the antineoplastic drug may be necessary. |
| Idelalisib | Idelalisib Cmax (↑), AUC (↑)2 Itraconazole serum conc. increase | USE WITH CAUTION, monitor for adverse reactions related |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| (extent unknown)2,3 | to itraconazole and/or idelalisib4, dose reduction of itraconazole and/or idelalisib may be necessary. | |
Axitinib Bosutinib Cabazitaxel Cabozantinib Ceritinib Cobimetinib Crizotinib Dabrafenib Dasatinib Docetaxel Entrectinib Glasdegib Ibrutinib Lapatinib Nilotinib Olaparib Pazopanib Sunitinib Talazoparib Trabectedin Trastuzumab emtansine Vinca alkaloids | Axitinib Cmax (↑), AUC (↑↑)2 Bosutinib Cmax (↑↑↑), AUC (↑↑↑)2 Cabazitaxel Cmax (↔), AUC (↔)2 Cabozantinib Cmax (↔), AUC (↑)2 Ceritinib Cmax (↑), AUC (↑↑)2 Cobimetinib Cmax ↑↑, AUC ↑↑↑ Crizotinib Cmax (↑), AUC (↑↑)2 Dabrafenib AUC (↑)2 Dasatinib Cmax (↑↑), AUC (↑↑)2 Docetaxel AUC (↔ to ↑↑)2 Entrectinib Cmax ↑, AUC ↑↑↑ Glasdegib Cmax (↑), AUC (↑↑)2 Ibrutinib Cmax (↑↑↑↑), AUC (↑↑↑↑)2 Lapatinib Cmax (↑↑), AUC (↑↑)2 Nilotinib Cmax (↑), AUC (↑↑)2 Olaparib Cmax ↑, AUC ↑↑ Pazopanib Cmax (↑), AUC (↑)2 Sunitinib Cmax (↑), AUC (↑)2 Talazoparib Cmax ↑, AUC ↑ Trabectedin Cmax (↑), AUC (↑)2 Trastuzumab emtasine conc. increase (extent unknown)2,3 Vinca alkaloid conc. increase (extent unknown)2,3 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of adverse reactions related to the antineoplastic drug4. Additionally: For cabazitaxel, even though the change in pharmacokinetic parameters did not reach statistical significance in a low-dose drug interaction study with ketoconazole, a high variability in the results was observed. For entrectinib, refer to the Product Monograph for specific actions to be taken. For ibrutinib, refer to the Product Monograph for specific actions to be taken. |
| Regorafenib | Regorafenib AUC (↓↓ by estimation of active moiety)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Regorafenib efficacy may be reduced. |
| Irinotecan | Irinotecan and its active metabolite conc. increase (extent unknown)2,3 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of irinotecan-related |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| adverse reactions, such as potentially life-threatening myelosuppression and diarrhea. | ||
| Venetoclax | Venetoclax Cmax (↑↑↑), AUC (↑↑↑)2 | CONTRAINDICATED for chronic lymphocytic leukemia/small lymphocytic lymphoma patients during dose initiation/titration/ramp- up phase of venetoclax. Otherwise, NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole4. |
| Antipsychotics, Anxiolytics and Hypnotics | ||
| Alprazolam Aripiprazole Brotizolam Buspirone Haloperidol Midazolam (iv) Perospirone Quetiapine Ramelteon Risperidone Zopiclone | Alprazolam Cmax ↔, AUC ↑↑ Aripiprazole Cmax ↑, AUC ↑ Brotizolam Cmax ↔, AUC ↑↑ Buspirone Cmax ↑↑↑↑, AUC ↑↑↑↑ Haloperidol Cmax ↑, AUC ↑ Midazolam (iv) conc. increase ↑↑3 Perospirone Cmax ↑↑↑, AUC ↑↑↑ Quetiapine Cmax (↑↑), AUC (↑↑↑)2 Ramelteon Cmax (↑), AUC (↑)2 Risperidone conc. increase ↑3 Zopiclone Cmax ↑, AUC ↑ | USE WITH CAUTION, monitor for adverse reactions related to the antipsychotic, anxiolytic or hypnotic drug4, dose reduction of these drugs may be necessary. |
| Lurasidone | Lurasidone Cmax (↑↑↑), AUC (↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of lurasidone-related adverse reactions, such as hypotension, circulatory collapse, severe extrapyramidal symptoms, seizures. |
| Pimozide | Pimozide Cmax (↑), AUC (↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of pimozide-related |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| adverse reactions, such as cardiac arrhythmias, possibly associated with QT prolongation and TdP. | ||
| Triazolam | Triazolam Cmax ↑ to ↑↑, AUC ↑↑ to ↑↑↑↑ | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of triazolam-related adverse reactions, such as seizures, respiratory depression, angioedema, apnea and coma. |
| Antivirals | ||
| Asunaprevir (boosted) | Asunaprevir Cmax (↑↑↑), AUC (↑↑↑)2 | CONTRAINDICATED, refer to the PM of the antiviral drug for specific actions to be taken. |
| Tenofovir disoproxil fumarate (TDF) | Tenofovir conc. increase (extent unknown)2,3 | USE WITH CAUTION, however, refer to the PM of the antiviral drug for specific actions to be taken. |
| Cobicistat | Cobicistat conc. increase (extent unknown)2,3 Itraconazole conc. increase (extent unknown)2,3 | USE WITH CAUTION, monitor for adverse reactions related to itraconazole, dose reduction of itraconazole may be necessary. |
| Daclatasvir | Daclatasvir Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for daclatasvir adverse reactions4, dose reduction of daclatasvir may be necessary. |
Darunavir (boosted) Fosamprenavir (ritonavir- boosted) | Ritonavir-boosted darunavir: itraconazole C Cmax (↑↑), AUC (↑↑)2 Ritonavir-boosted fosamprenavir: itraconazole Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for itraconazole adverse reactions, dose reduction of itraconazole may be necessary. |
| Elvitegravir (boosted) | Elvitegravir Cmax (↑), AUC (↑)2 Itraconazole conc. increase (extent unknown)2,3 | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or elvitegravir (ritonavir-boosted)4. Dose reduction of itraconazole may be necessary; refer to the elvitegravir PM for |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| specific actions to be taken. | ||
Efavirenz Nevirapine | Efavirenz: itraconazole Cmax ↓, AUC ↓ Nevirapine: itraconazole Cmax ↓, AUC ↓↓ | NOT RECOMMENDED from 2 weeks before and during treatment with itraconazole. Itraconazole efficacy may be reduced. |
| Elbasvir/Grazoprevir | Elbasvir Cmax (↔), AUC (↑)2 Grazoprevir Cmax (↔), AUC (↑↑)2 | USE WITH CAUTION, monitor for adverse reactions related to the co- administered drugs4. Refer to the elbasvir/grazoprevir PM for specific actions to be taken. |
| Glecaprevir/Pibrenta svir | Glecaprevir Cmax (↑↑), AUC (↑↑ to ↑↑↑)2 Pibrentasvir Cmax (↔ to ↑), AUC (↔ to ↑↑)2 | USE WITH CAUTION, monitor for adverse reactions related to the co- administered drugs4. Refer to the glecaprevir/pibrentasvir PM for specific actions to be taken. |
| Indinavir | Itraconazole conc. ↑3 Indinavir Cmax ↔, AUC ↑ | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or indinavir4, dose reduction of itraconazole and/or indinavir may be necessary. |
| Maraviroc | Maraviroc Cmax (↑↑), AUC (↑↑↑)2 | USE WITH CAUTION monitor for adverse reactions4. Dose reduction of maraviroc may be necessary. |
| Ritonavir | Itraconazole Cmax (↑), AUC (↑↑)2 Ritonavir Cmax (↔), AUC (↑)2 | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or ritonavir4, Dose reduction of itraconazole may be necessary; refer to the ritonavir PM for specific actions to be taken. |
| Saquinavir | Saquinavir (unboosted) Cmax ↑↑, AUC ↑↑↑ Itraconazole (with boosted saquinavir) Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or saquinavir4, Dose reduction of itraconazole may be necessary; refer to the saquinavir PM for |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| specific actions to be taken. | ||
| Beta Blockers | ||
| Nadolol | Nadolol Cmax ↑↑, AUC ↑↑ | USE WITH CAUTION, monitor for nadolol adverse reactions4. Dose reduction of nadolol may be necessary. |
| Calcium Channel Blockers | ||
| Diltiazem | Diltiazem & Itraconazole conc. Increase (extent unknown)2,3 | USE WITH CAUTION, monitor for adverse reactions related to itraconazole and/or diltiazem4, dose reduction of itraconazole and/or diltiazem may be necessary. |
| Felodipine | Felodipine Cmax ↑↑↑, AUC ↑↑↑ | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of dihydropyridine-related adverse reactions, such as hypotension and peripheral edema. |
| Other dihydropyridines Verapamil | Dihydropyridine conc. Increase (extent unknown)2,3 Verapamil conc. Increase (extent unknown)2,3 | USE WITH CAUTION, monitor for dihydropyridine/verapamil adverse reactions4, dose reduction of dihydropyridine/verapamil may be necessary. |
| Cardiovascular Drugs | ||
Aliskiren Riociguat Sildenafil (pulmonary hypertension) Tadalafil (pulmonary hypertension) | Aliskiren Cmax ↑↑↑, AUC ↑↑↑ Riociguat Cmax (↑), AUC (↑↑)2 Sildenafil/Tadalafil conc. increase (extent unknown but effect may be greater than reported under Urologic Drugs)2,3 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole4. Increased risk of adverse reactions related to the cardiovascular drug. |
| Bosentan Guanfacine | Bosentan Cmax (↑↑), AUC (↑↑)2 Guanfacine Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for bosentan/guanfacine adverse reactions4, dose reduction of bosentan/guanfacine may be necessary. |
| Ivabradine | Ivabradine Cmax (↑↑), AUC (↑↑↑)2 | CONTRAINDICATED during and |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| for 2 weeks after treatment with itraconazole. Increased risk of ivabradine-related adverse reactions, such as atrial fibrillation, bradycardia, sinus arrest and heart block. | ||
| Ranolazine | Ranolazine Cmax (↑↑), AUC (↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of ranolazine-related adverse reactions, such as QT prolongation and renal failure. |
| Contraceptives1 | ||
Dienogest Ulipristal | Dienogest Cmax (↑), AUC (↑↑)2 Ulipristal Cmax (↑↑), AUC (↑↑↑)2 | USE WITH CAUTION, monitor for contraceptive adverse reactions4, refer to the dienogest/ulipristal PM for specific actions to be taken. |
| Diuretics | ||
| Eplerenone | Eplerenone Cmax (↑), AUC (↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of eplerenone-related adverse reactions, such as hyperkalemia and hypotension. |
| Gastrointestinal Drugs | ||
| Aprepitant Loperamide Netupitant | Aprepitant AUC (↑↑↑)2 Loperamide Cmax ↑↑, AUC ↑↑ Netupitant Cmax (↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for aprepitant/loperamide/netupit ant adverse reactions4, Dose reduction of aprepitant/loperamide may be necessary. Refer to the netupitant Product Monograph for specific actions to be taken. |
| Domperidone | Domperidone Cmax ↑↑, AUC ↑↑ | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of domperidone-related |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| adverse reactions, such as serious ventricular arrhythmias and sudden cardiac death. | ||
| Naloxegol | Naloxegol Cmax (↑↑↑), AUC (↑↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of naloxegol-related adverse reactions, such as opioid withdrawal symptoms. |
| Saccharomyces boulardii | S. boulardii colonization decrease (extent unknown) | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. S. boulardii efficacy may be reduced. |
| Immunosuppressants | ||
Budesonide Ciclesonide Cyclosporine Dexamethasone Fluticasone Methylprednisolone Tacrolimus Temsirolimus | Budesonide (inhalation) Cmax ↑, AUC ↑↑; Budesonide (other form) conc. increase (extent unknown)2,3 Ciclesonide (inhalation) Cmax (↑↑), AUC (↑↑)2 Cyclosporine (iv) conc. increase ↔ to ↑3 Cyclosporine (other form) conc. increase (extent unknown)2,3 Dexamethasone Cmax ↔ (iv) ↑ (oral), AUC ↑↑ (iv, oral) Fluticasone (inhalation) conc. increase ↑↑3 Fluticasone (nasal) conc. increase (↑)2,3 Methylprednisolone (oral) Cmax ↑ to ↑↑, AUC ↑↑ Methylprednisolone (iv) AUC ↑↑ Tacrolimus (iv) conc. increase ↑3 Tacrolimus (oral) Cmax (↑↑), AUC (↑↑)2 Temsirolimus (iv) Cmax (↑↑), AUC (↑↑)2 | USE WITH CAUTION monitor for immunosuppressant adverse reactions4, Dose reduction of the immunosuppressant drug may be necessary. |
Everolimus Sirolimus | Everolimus Cmax (↑↑), AUC (↑↑↑↑)2 | NOT RECOMMENDED during and for 2 weeks after |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| (rapamycin) | Sirolimus Cmax (↑↑), AUC (↑↑↑↑)2 | treatment with itraconazole4. Increased risk of everolimus/ sirolimus-related adverse reactions. |
| Lipid Regulating Drugs | ||
| Atorvastatin | Atorvastatin Cmax ↔ to ↑↑, AUC ↑ to↑↑ | USE WITH CAUTION, monitor for atorvastatin adverse reactions4. Dose reduction of atorvastatin may be necessary. |
| Lomitapide | Lomitapide Cmax (↑↑↑↑), AUC (↑↑↑↑)2 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of lomitapide-related adverse reactions, such as hepatotoxicity and severe gastrointestinal reactions. |
| Lovastatin Simvastatin | Lovastatin Cmax ↑↑↑↑, AUC ↑↑↑↑ Simvastatin Cmax ↑↑↑↑, AUC ↑↑↑↑ | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of lovastatin/simvastatin-related adverse reactions, such as myopathy, rhabdomyolysis and liver enzyme abnormalities. |
| Nonsteroidal Anti-Inflammatory Drugs | ||
| Meloxicam | Meloxicam Cmax ↓↓, AUC ↓ | USE WITH CAUTION, monitor for reduced efficacy of meloxicam, dose adaption of meloxicam may be necessary. |
| Respiratory Drugs | ||
| Salmeterol | Salmeterol Cmax (↑), AUC (↑↑↑↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of salmeterol-related adverse reactions4. |
| SSRIs, Tricyclics and Related Antidepressants | ||
| Reboxetine | Reboxetine Cmax (↔), AUC (↑)2 | USE WITH CAUTION, monitor |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| Venlafaxine | Venlafaxine Cmax (↑), AUC (↑)2 | for reboxetine/venlafaxine adverse reactions4, dose reduction of reboxetine/venlafaxine may be necessary. |
| Urologic Drugs | ||
| Darifenacin Vardenafil | Darifenacin Cmax (↑↑↑), AUC (↑↑↑ to ↑↑↑↑)2 Vardenafil Cmax (↑↑), AUC (↑↑↑↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of darifenacin/vardenafil-related adverse reactions4. |
Dutasteride Imidafenacin Oxybutynin Sildenafil (erectile dysfunction) Tadalafil (erectile dysfunction and benign prostatic hyperplasia) Tolterodine | Dutasteride conc. increase (extent unknown)2,3 Imidafenacin Cmax ↑, AUC ↑ Oxybutynin conc. increase ↑3 Sildenafil Cmax (↑↑), AUC (↑↑ to ↑↑↑↑)2 Tadalafil Cmax (↑), AUC (↑↑)2 Tolterodine Cmax (↑ to ↑↑), AUC (↑↑)2 in poor metabolizers of CYP2D6 | USE WITH CAUTION, monitor for urologic drug adverse reactions4, dose reduction of the urologic drug may be necessary; refer to the dutasteride PM for specific actions to be taken. (For sildenafil and tadalafil, see also Cardiovascular Drugs, Miscellaneous Drugs and Other Substances in this table.) |
| Fesoterodine | Fesoterodine Cmax (↑↑), AUC (↑↑)2 | CONTRAINDICATED in patients with moderate to severe renal or hepatic impairment, during and for 2 weeks after treatment with itraconazole. Increased risk of fesoterodine-related adverse reactions, such as severe anticholinergic effects. USE WITH CAUTION in other patients: monitor for fesoterodine adverse reactions4, dose reduction of fesoterodine may be necessary. |
| Solifenacin | Solifenacin Cmax (↑), AUC (↑↑)2 | CONTRAINDICATED in patients with severe renal or moderate |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
to severe hepatic impairment, during and for 2 weeks after treatment with itraconazole. Increased risk of solifenacin-related adverse reactions, such as anticholinergic effects and QT prolongation. USE WITH CAUTION in other patients, monitor for solifenacin drug adverse reactions4, dose reduction of solifenacin may be necessary. | ||
| Miscellaneous Drugs and Other Substances | ||
Alitretinoin (oral) Cabergoline Cannabinoids Cinacalcet | Alitretinoin Cmax (↑), AUC (↑)2 Cabergoline Cmax (↑↑), AUC (↑↑)2 Cannabinoids conc increase, extent unknown but likely (↑↑)2 Cinacalcet Cmax (↑↑), AUC (↑↑)2 | USE WITH CAUTION, monitor for alitretinoin/cabergoline/canna binoids/ cinacalcet drug adverse reactions, dose reduction of alitretinoin/cabergoline/canna binoids/cinacalcet may be necessary4. |
| Colchicine | Colchicine Cmax (↑), AUC (↑↑)2 | CONTRAINDICATED in patients with renal or hepatic impairment, during and for 2 weeks after treatment with itraconazole. Increased risk of colchicine-related adverse reactions, such as decreased cardiac output, cardiac arrhythmias, respiratory distress and bone marrow depression. NOT RECOMMENDED in other patients, during and for 2 weeks after treatment with itraconazole. Increased risk of colchicine-related adverse reactions4. |
| Eliglustat | CYP2D6 EMs: Eliglustat Cmax (↑↑), | CONTRAINDICATED in CYP2D6 EMs taking a strong or |
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
AUC (↑↑)2 Higher increases are expected in CYP2D6 IMs/PMs and upon coadministration with a CYP2D6 inhibitor. | moderate CYP2D6 inhibitor/CYP2D6 IMs and PMs, during and for 2 weeks after treatment with itraconazole. Increased risk of eliglustat-related adverse reactions such as prolongation of the PR, QTc, and/or QRS cardiac interval, and cardiac arrhythmias. USE WITH CAUTION in CYP2D6 EMs, monitor for eliglustat adverse reactions4, dose reduction of eliglustat may be necessary. | |
| Ergot alkaloids | Ergot alkaloids conc. increase (extent unknown)2,3 | CONTRAINDICATED during and for 2 weeks after treatment with itraconazole. Increased risk of ergot alkaloid-related adverse reactions, such as ergotism. (see also Antimigraine Drugs in this table) |
| Galantamine | Galantamine Cmax (↑), AUC (↑)2 | USE WITH CAUTION, monitor for galantamine adverse reactions4. Dose reduction of galantamine may be necessary. |
| Ivacaftor | Ivacaftor Cmax (↑↑), AUC (↑↑↑)2 | USE WITH CAUTION, monitor for ivacaftor adverse reactions4, dose reduction of ivacaftor may be necessary. |
| Lumacaftor/Ivacaftor | Ivacaftor Cmax (↑↑), AUC (↑↑)2 Lumacaftor Cmax (↔), AUC (↔)2 Itraconazole conc decrease, extent unknown but likely ↓↓↓ | NOT RECOMMENDED from 2 weeks before, during and for 2 weeks after treatment with itraconazole. Itraconazole efficacy may be reduced and increased risk of ivacaftor-related adverse reactions4. |
| Vasopressin Receptor Antagonists | ||
| Examples of medicinal products within class | Expected/Potential effect on drug levels (see footnotes for additional info) | Clinical comment (see codes above for additional info) |
|---|---|---|
| Conivaptan Tolvaptan | Conivaptan Cmax (↑↑), AUC (↑↑↑↑)2 Tolvaptan Cmax (↑↑), AUC (↑↑↑)2 | NOT RECOMMENDED during and for 2 weeks after treatment with itraconazole. Increased risk of conivaptan/ tolvaptan-related adverse reactions4. |
| Mozavaptan | Mozavaptan Cmax ↑, AUC ↑↑ | USE WITH CAUTION, monitor for mozavaptan adverse reactions4, dose reduction of mozavaptan may be necessary. |
EMs: extensive metabolizers; IMs: intermediate metabolizers; PMs: poor metabolizers; TdP: Torsade de Pointes
Note:
Average increase:
↑: <100% (i.e. <2-fold);
↑↑: 100-400% (i.e. ≥2-fold to <5-fold);
↑↑↑: 400-900% (i.e. ≥5-fold and <10-fold);
↑↑↑↑: ≥10-fold;
Average decrease:
↓: <40%;
↓↓: 40-80%;
↓↓↓: >80%;
No effect: ↔
For the effect (middle column) the name of the parent drug is stated, even when the effect is related to the active moiety or the active metabolite of a prodrug.
- 1. CYP3A4 inhibitors (including itraconazole) may increase systemic contraceptive hormone concentrations
- 2. For drugs with arrows between brackets, the assessment was based on the mechanism of interaction and clinical drug interaction information with ketoconazole or other strong CYP3A4 inhibitors and/or inhibitors of P- glycoprotein or BCRP, modelling techniques, case reports and/or in vitro data. For the other drugs listed, the assessment was based on clinical drug interaction information with itraconazole.
- 3. Pharmacokinetic parameters were not available.
- 4. Please consult the corresponding Product Monograph (PM) for information on drug-related adverse reactions
9.5 Drug-Food Interactions
For optimal absorption, JAMP Itraconazole Oral Solution should be taken without food (see 10.3 Pharmacokinetics).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Itraconazole, a triazole derivative, has a broad-spectrum activity; with respect to Candida spp., its activity includes C. albicans, C. glabrata and C. krusei.
In vitro studies have demonstrated that itraconazole impairs the synthesis of ergosterol in fungal cells. Ergosterol is a vital cell membrane component in fungi. Impairment of its synthesis ultimately results in an antifungal effect.
10.2 Pharmacodynamics Human Pharmacodynamics
In vitro
A 50% inhibition of the cholesterol biosynthesis is obtained in vitro in human lymphocytes with itraconazole at a concentration of 4 x 10⁻⁷M, which is more than 100 times the concentration of itraconazole needed to produce a 50% inhibition of the ergosterol synthesis in Candida albicans.
Up to a concentration of 10-5M, itraconazole did not inhibit the cytochrome P450 dependent aromatization of androstenedione to estrogens by human placental microsomes.
In vivo
In male volunteers, basal serum levels of cholesterol remained similar to the control values obtained before itraconazole treatment of 100 mg o.d. for 1 month.
Long-term administration of itraconazole (up to 400 mg/day for up to a maximum of 2 years) indicated a slight decrease in plasma cholesterol in 67 patients who had a baseline cholesterol plasma level higher than 200 mg/dL.
Only 9.5% of patients showed a shift to a somewhat higher plasma cholesterol level. Similar results were observed in 29 patients with baseline cholesterol levels of at least 250 mg/dL and itraconazole therapy (50-400 mg/day) for a minimum of 3 months. Twenty-three patients showed a reduction and six patients had an increased cholesterol level. In this study, the overall decrease in cholesterol did not coincide with alterations in the triglyceride levels.
There was no significant effect of itraconazole 100 or 200 mg taken daily for 35 days on the serum levels of 25-hydroxycholecalciferol and 1,25-dihydroxycholecalciferol in 12 volunteers.
In volunteers receiving single or multiple doses of itraconazole for up to 30 days, no effect on serum levels of the following hormones were observed: basal plasma cortisol, testosterone, aldosterone, cortisol response to cosyntropin (ACTH) and plasma prolactin and response of plasma prolactin, follicle stimulating hormone (FSH) and luteinizing hormone (LH) to an intravenous luteinizing hormone releasing hormone (LHRH) challenge.
Plasma progesterone and estradiol levels measured once weekly (before, during and for 2 weeks after a 5-week administration period of itraconazole 200 mg/day) and saliva progesterone concentrations measured daily during the 5-week administration, reflected a totally normal hormonal profile throughout the menstrual cycle.
In healthy female volunteers with normal, regular menstrual cycles, a single 300 mg dose of itraconazole taken during the late follicular phase did not modify the circadian variation in plasma 17β-estradiol levels. The same dose taken during the luteal phase had no effects on 17β-estradiol and progesterone levels.
Male patients with superficial mycoses who received 50 or 100 mg itraconazole for up to
2 months showed no change in levels of testosterone, sex hormone binding globulin (SHBG), luteinizing hormone (LH), follicle stimulating hormone (FSH) and estradiol.
In 15 patients with systemic mycoses receiving 200 to 400 mg/day itraconazole, adrenal function was studied before and after 12.4 ± 5 (7-24) months of treatment. No change in the response of plasma cortisol to ACTH stimulation was observed. Average testosterone values measured in these patients before and after itraconazole were not statistically significantly different. However, one of eight patients treated with itraconazole 600 mg/day for severe or refractory systemic fungal infection demonstrated a blunted cortisol response after one month of treatment. Reduction of the dose to 400 mg/day was associated with resolution of the symptoms associated with adrenal insufficiency and an improved cortisol response.
The administration of 200 mg itraconazole daily for 5 weeks had no significant influence on the heart rate, blood pressure, ECG intervals and systolic time intervals in volunteers. This finding was confirmed in cancer patients who received 50 mg itraconazole daily for 48 weeks.
In six healthy volunteers, itraconazole 200 mg daily did not seem to have a negative influence on immune functions. After 5 weeks of itraconazole treatment, only values for OKT4 positive lymphocyte showed a significant shift from 42 ± 3.3% to 53 ± 3.3%. This increase as well as shifts in the other immunological parameters remained within the normal ranges.
Animal Pharmacodynamics
In general observation tests, the dose of 40 mg/kg, given orally to mice and injected intraperitoneally in rats, was devoid of central actions. In addition, many peripheral (anticholinergic, antidiarrheal, α1-adrenergic blocking, muscle relaxant, aspirin-like activation) and non-specific actions (hypothermic, toxic) can be excluded from its activity profile.
Itraconazole, at the oral dose of 40 mg/kg in rats was found to be devoid of effects on: conditioned food consumption; fecal excretion; urine excretion; castor oil diarrhea; tail withdrawal reaction time; Mycobacterium butyricum arthritis (36 mg/kg in the food); and gastric mucosal integrity (40 mg/mL or 100 mg/kg in 0.15 M HCl). Whenever any effects of itraconazole dissolved in PEG 200 were observed, they were identical to those seen with the vehicle alone.
10.3 Pharmacokinetics
Absorption
The oral bioavailability of itraconazole is maximal when JAMP Itraconazole Oral Solution is taken without food. During chronic administration, steady-state is reached after 1-2 weeks. Peak plasma levels are observed 2 hours (fasting) to 5 hours (with food) following administration of the oral solution. After repeated once-a-day administration of itraconazole 200 mg in fasting condition, steady-state plasma concentrations of itraconazole fluctuate between 1 and 2 mcg/mL (trough to peak). When the oral solution is taken with food, steady-state plasma concentrations of itraconazole are about 25% lower.
The absolute bioavailability of itraconazole administered as a non-marketed solution formulation under fed conditions was 55% in six healthy male volunteers. However, the bioavailability of itraconazole oral solution is increased under fasted conditions reaching higher maximum plasma concentrations (Cmax) in a shorter period of time. In 27 healthy male volunteers, the steady-state area under the plasma concentration versus time curve (AUC0-24) of itraconazole (itraconazole oral solution, 200 mg daily for 15 days) under fasted conditions was 131 ± 30% of that obtained under fed conditions. Therefore, unlike itraconazole capsules, it is recommended that itraconazole oral solution be administered without food. Presented in Table 5 below are the steady-state (Day 15) pharmacokinetic parameters for itraconazole and hydroxy-itraconazole (itraconazole oral solution) under fasted and fed conditions.
Table 5: Steady-state pharmacokinetic parameters for itraconazole and hydroxy- itraconazole under fasted and fed conditions.
| Itraconazole | Hydroxy-itraconazole | |||
|---|---|---|---|---|
| Fasted | Fed | Fasted | Fed | |
| Cmax (ng/mL) | 1963 ± 6011 | 1435 ± 477 | 2055 ± 487 | 1781 ± 397 |
| Tmax (hours) | 2.5 ± 0.8 | 4.4 ± 0.7 | 5.3 ± 4.3 | 4.3 ± 1.2 |
| AUC0-24 (ng.h/mL) | 29271 ± 10285 | 22815 ± 7098 | 45184 ± 10981 | 38823 ± 8907 |
| t1/2 (hours) | 39.7 ± 13 | 37.4 ± 13 | 27.3 ± 13 | 26.1 ± 10 |
- 1. mean ± standard deviation
Itraconazole exposure is greater with the oral solution than with the capsule formulation when the same dose of drug is given.
The bioavailability of itraconazole oral solution relative to itraconazole capsules was studied in 30 healthy male volunteers who received 200 mg of itraconazole as the oral solution and capsules under fed conditions. The AUC0-∞ from itraconazole oral solution was 149 ± 68% of that obtained from itraconazole capsules; a similar increase was observed for hydroxy- itraconazole. In addition, a cross-study comparison of itraconazole and hydroxy-itraconazole pharmacokinetics following the administration of single 200 mg doses of itraconazole oral solution (under fasted conditions) or itraconazole capsules (under fed conditions) indicates that when these two formulations are administered under conditions which optimize their systemic absorption, the bioavailability of the solution relative to capsules is expected to be increased further. Therefore, it is recommended that itraconazole oral solution and itraconazole capsules not be used interchangeably. Table 6 contains pharmacokinetic parameters for itraconazole and hydroxy-itraconazole following single 200 mg doses of itraconazole oral solution (n=27) or itraconazole capsules (n=30) administered to healthy male volunteers under fasted and fed conditions, respectively.
Table 6: Pharmacokinetic parameters for itraconazole and hydroxy-itraconazole in healthy male volunteers under fed and fasted conditions
| Itraconazole | Hydroxy-itraconazole | |||
|---|---|---|---|---|
| Oral Solution fasted | Capsules fed | Oral Solution fasted | Capsules fed | |
| Cmax (ng/mL) | 544 ± 2131 | 302 ± 119 | 622 ± 116 | 504 ± 132 |
| Tmax (hours) | 2.2 ± 0.8 | 5 ± 0.8 | 3.5 ± 1.2 | 5 ± 1 |
| AUC0-24 (ng.h/mL) | 4505 ± 1670 | 2682 ± 1084 | 9552 ± 1835 | 7293 ± 2144 |
- 1. mean ± standard deviation
Distribution
The plasma protein binding of itraconazole is 99.8% and that of hydroxy-itraconazole is 99.5%.
Itraconazole is extensively distributed into tissues that are prone to fungal invasion. Concentrations in human lung, kidney, liver, bone, stomach, spleen and muscle were found to be two to three times higher than the corresponding plasma concentrations. Concentrations in the cerebrospinal fluid are much lower than in plasma. Concentrations of itraconazole in whole blood are 60% of those in plasma. Uptake in keratinous tissues, especially the skin, is up to five times higher than in plasma, and elimination of itraconazole is related to epidermal regeneration. Therefore, therapeutic levels in the skin persist for 2 to 4 weeks after discontinuation of a 4-week treatment. Itraconazole is also present in sebum and to a lesser extent in sweat.
Metabolism
Itraconazole is extensively metabolized by the liver into a large number of metabolites. In vitro studies have shown that CYP3A4 is the major enzyme involved in the metabolism of itraconazole. The main metabolite is hydroxy-itraconazole, which has in vitro a comparable antifungal activity to itraconazole. Antifungal drug levels measured by bioassay were about three times those of itraconazole assayed by high-performance liquid chromatography. Trough plasma levels of hydroxy-itraconazole are about two times higher than those of itraconazole.
The main metabolic pathways were oxidative scission of the dioxolane ring, aliphatic oxidation at the 1-methylpropyl substituent, N-dealkylation of this 1-methylpropyl substituent, oxidative degradation of the piperazine ring and triazolone scission.
Excretion
Itraconazole is excreted mainly as inactive metabolites in urine (35%) and in feces (54%) within one week of an oral solution dose. Renal excretion of itraconazole and the active metabolite hydroxy-itraconazole account for less than 1% of an intravenous dose. After repeated oral administration, elimination of itraconazole from plasma is biphasic with a terminal half-life of 1.5 days. Based on an oral radiolabelled dose, fecal excretion of the unchanged drug ranges from 3%-18% of the dose. Renal excretion of the parent drug is less than 0.03% of the dose. One week after oral administration of radiolabelled itraconazole, urinary excretion of total radioactivity amounted to 35% of the dose and fecal excretion represented 54% of the dose.
As re-distribution of itraconazole from keratinous tissues appears to be negligible, elimination of itraconazole from these tissues is related to epidermal regeneration. Contrary to plasma, the concentration in skin persists for 2 to 4 weeks after discontinuation of a 4-week treatment and in nail keratin – where itraconazole can be detected as early as 1 week after start of treatment – for at least six months after the end of a 3-month treatment period.
Special Populations and Conditions Pediatrics
Limited pharmacokinetic data are available on the use of itraconazole in the pediatric population. A clinical pharmacokinetic of itraconazole oral solution were studied in 26 children and adolescents aged between 6 months and 12 years requiring systemic antifungal therapy.
Patients were stratified by age: 6 months to 2 years (n=8), 2 to 5 years (n=7) and 5 to 12 years (n=11) and received itraconazole oral solution 5 mg/kg once daily for 14 days.
Pharmacokinetic parameters at steady state (Day 14) were not significantly different among the age strata and are summarized in Table 7 below for all 26 patients.
Table 7: Pharmacokinetics of itraconazole oral solution in pediatric patients
| Itraconazole | Hydroxy-itraconazole | |
|---|---|---|
| Cmax (ng/mL) | 582.5 ± 382.41 | 692.4 ± 355.0 |
| Cmin (ng/mL) | 187.5 ± 161.4 | 403.8 ± 336.1 |
| AUC0-24 (ng.h/mL) | 7706.7 ± 5245.2 | 13356.4 ± 8942.4 |
| t1/2 (hours) | 35.8 ± 35.6 | 17.7 ± 13.0 |
- 1. mean ± standard deviation
Geriatrics
No data are available in geriatric patients.
Hepatic Insufficiency
Itraconazole is predominantly metabolized in the liver. Pharmacokinetic data for patients with hepatic insufficiency is limited to subjects who received a single 100 mg dose of itraconazole capsules. A pharmacokinetic study using a single 100 mg dose of itraconazole (one 100 mg capsule) was conducted in 6 healthy and 12 cirrhotic subjects. A statistically significant reduction in mean Cmax (47%; mean cirrhotic Cmax 87 ± 18 ng/mL, mean healthy Cmax 164 ± 34 ng/mL) and a two-fold increase in the elimination half-life (37 ± 7 hrs and 16 ± 5 hrs, respectively) of itraconazole were noted in cirrhotic subjects compared with healthy subjects.
However, overall exposure to itraconazole, based on AUC was similar in cirrhotic patients and in healthy subjects (mean cirrhotic AUC 1449 ± 207 ng.h/mL, mean healthy AUC 1856 ±
388 ng.h/mL). Data are not available in cirrhotic patients during long-term use of itraconazole. Patients with impaired hepatic function should be carefully monitored when taking itraconazole. The prolonged elimination half-life of itraconazole observed in cirrhotic patients should be considered when deciding to initiate therapy with other medicines metabolized by CYP3A4 (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic, Use in Patients Hepatic Insufficiency).
Renal Insufficiency
Limited data are available on the use of itraconazole in patients with renal insufficiency. Pharmacokinetic data in renally impaired patients is limited to subjects who received a single 200 mg dose of itraconazole capsules. A pharmacokinetic study using a single 200 mg dose of itraconazole (four 50 mg capsules) was conducted in three groups of patients with renal impairment (uremia: n=7; hemodialysis: n=7; continuous ambulatory peritoneal dialysis: n=5).
Mean ± SD pharmacokinetic parameters are summarized in Table 8.
Table 8: Mean pharmacokinetic parameters in renally impaired patients receiving a single 200 mg oral dose of itraconazole
| Patient Group (n) | Tmax (h) | Cmax (ng/mL) | AUC0-8h (ng.h/mL) |
|---|---|---|---|
| Uremic (7) | 4.0 ± 1.2 | 213 ± 178 | 1026 ± 819 |
| Hemodialysis | |||
| Off dialysis (7) | 4.7 ± 1.4 | 140 ± 119 | 634 ± 507 |
| On dialysis (7) | 4.1 ± 0.9 | 113 ± 83 | 507 ± 371 |
| CAPD (5) | 4.4 ± 2.2 | 77 ± 29 | 325 ± 107 |
Plasma concentration vs. time profiles showed wide inter-subject variation in all three groups. In uremic subjects (mean CrCl 13 mL/min/1.73m2), mean plasma concentrations and overall exposure, based on AUC , were slightly reduced compared with healthy subject in a previous study (AUC values of 3454 ± 3132 vs. 4161 ± 1949 ng.h/mL in uremic patients and healthy subjects, respectively). Cmax and AUC0-8h values were reduced 30-40% in hemodialysis patients on non-dialysis days, compared to uremic patients (see Table 8), and further reduced 10-20% on dialysis days. In CAPD patients, Cmax and AUC0-8h values were reduced to one-third the values seen in non-dialyzed uremic patients.
Data are not available in renally impaired patients during long-term use of itraconazole. Dialysis has no effect on the half-life or clearance of itraconazole or hydroxy-itraconazole (see
7 WARNINGS AND PRECAUTIONS, Renal, Use in Patients with Renal Insufficiency and
4.2 Recommended Dose and Dosage Adjustment, Special Populations, Patients with Renal Impairment).
Cystic Fibrosis
In cystic fibrosis patients, variability in therapeutic levels of itraconazole was observed with steady-state dosing of oral solution using 2.5 mg/kg b.i.d. Steady-state concentrations of
>250 ng/mL were achieved in approximately 50% of subjects greater than 16 years of age, but in none of the patients less than 16 years of age. If a patient does not respond to JAMP Itraconazole Oral Solution, consideration should be given to switching to alternative therapy.
HIV-Positive Patients
The bioavailability of itraconazole oral solution was investigated in two groups of HIV-positive patients characterized by the severity of their HIV infection. The first group consisted of
12 patients with CD4 count >200/mm3 and no AIDS; the second group included 11 patients with CD4 count <100/mm3 and AIDS. At 100 mg b.i.d. for 15 days, both groups displayed satisfactory plasma concentrations and the bioavailability was equivalent in both groups. Table 9 summarizes the study results.
Table 9: Plasma concentrations (ng/mL) of itraconazole and hydroxy-itraconazole after repeated administration of itraconazole oral solution in HIV-positive patients
| Day | HIV-positive patients with CD4 count >200/mm3 | AIDS patients with CD4 count <100/mm3 | ||
|---|---|---|---|---|
| Itraconazole | Hydroxy- itraconazole | Itraconazole | Hydroxy- itraconazole | |
| 2 | 112 ± 451 | 310 ± 121 | 95 ± 84 | 258 ± 156 |
| 4 | 305 ± 93 | 771 ± 211 | 271 ± 189 | 688 ± 346 |
| 7 | 443 ± 189 | 1105 ± 343 | 424 ± 281 | 1034 ± 524 |
| 13 | 585 ± 250 | 1302 ± 511 | 587 ± 377 | 1339 ± 731 |
| 15 | 645 ± 303 | 1481 ± 563 | 583 ± 414 | 1355 ± 800 |
- 1. mean ± standard deviation
11 STORAGE, STABILITY AND DISPOSAL
JAMP Itraconazole Oral Solution should be stored at 15-25°C. Discard remaining unused product one month after opening bottle. Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Proper name: Itraconazole
Chemical name: (±)-cis-4-[4-[4-[4-[[2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1- ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1- piperazinyl]phenyl]-2,4-dihydro-2-(1-methylpropyl)-3H-1,2,4- triazol-3-one
Molecular formula and molecular mass: C35H38Cl2N8O4, 705.64 g/mol
Structural formula:
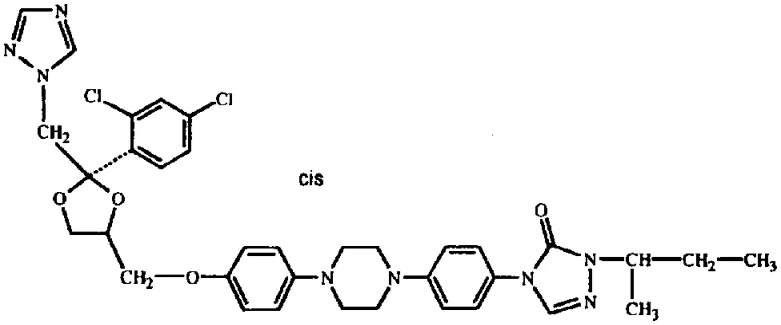
Physicochemical properties: Itraconazole is an almost white to slightly yellow powder, with a pKa of 3.7 and a melting range of 165-169°C. It is highly hydrophobic and lipophilic, with a log partition coefficient of 5.66 in the n-octanol/aqueous buffer solution of pH=8.1.
Itraconazole is very poorly soluble in water (<1 mcg/mL) and in diluted acidic solutions (<5 mcg/mL).
Concentrations exceeding 1% can only be obtained in some organic solvents such as acidified polyethylene glycols (PEG) or in aqueous cyclodextrin solutions.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Oropharyngeal Candidiasis
Table 10: Summary of patient demographics for clinical trials in oropharyngeal candidiasis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (total/efficacy)1 | Mean age (Range)2 | Sex (M/F)2 |
|---|---|---|---|---|---|
| ITR-USA-7 | third-party blinded, active- controlled | itraconazole oral solution 200 mg o.d. for 7 days itraconazole oral solution 200 mg o.d. for 14 days fluconazole tablet 100 mg o.d. for 14 days | n=64/60 n=64/59 n=62/60 | 38 (25-67) 36.5 (21-67) 37.5 (24-61) | 56/8 62/2 58/4 |
| ITR-INT-27 | itraconazole oral solution 100 mg b.i.d. for 7 days itraconazole oral solution 100 mg o.d. for 14 days fluconazole tablet 100 mg o.d. for 14 days | n=79/68 n=79/68 n=86/78 | 37 (22-64) 35 (24-58) 36 (21-66) | 72/7 70/9 79/7 | |
| ITR-USA-94 | uncontrolled, open-label | itraconazole oral solution, 100 mg b.i.d. for 14-28 days based on response | n=74/68 | 37 (20-60) | 68/6 |
- 1. Total: intent-to-treat population; Efficacy: patients included in efficacy analysis
- 2. Values based on total number of study subjects
Two randomized, controlled studies for the treatment of oropharyngeal candidiasis have been conducted. In one trial (n=179, all patients HIV-seropositive), clinical response (a global clinical evaluation of cured or improved) was not significantly different for patients treated with fluconazole tablets, 100 mg/day for 14 days (52/60; 87%), or itraconazole oral solution,
200 mg/day given for 7 days (50/60; 83%) or 14 days (57/59; 97%). Response to 14 days therapy with itraconazole oral solution was associated with a lower relapse rate than response to 7 days therapy with itraconazole oral solution. In the other trial (n=214, all HIV-seropositive patients), clinical response was not significantly different for patients treated with itraconazole oral solution 200 mg/day for 14 days, itraconazole oral solution 100 mg/day for 14 days or fluconazole 100 mg/day for 14 days. Response was 56/68 (84%), 62/68 (91%) and 71/78 (91%) for patients treated with a daily dose of itraconazole oral solution 200 mg, itraconazole oral solution 100 mg and fluconazole 100 mg, respectively.
In an uncontrolled, open-label study of selected patients clinically unresponsive to fluconazole tablets (n=74, all patients HIV-seropositive), patients were treated with itraconazole oral solution 100 mg b.i.d. (clinically unresponsive to fluconazole in this study was defined as having received a dose of fluconazole tablets at least 200 mg/day for a minimum of 14 days). Treatment duration was 14-28 days based on response.
The mean CD4 count of these patients was 23/mm3. Approximately 55% of patients had complete resolution of oral lesions. Of patients who responded and then entered a follow-up phase (n=22), all relapsed within a month when treatment was discontinued, with a median time to relapse of 14 days. Although baseline endoscopies had not been performed, several patients in this study developed symptoms of esophageal candidiasis while receiving treatment with itraconazole oral solution. Itraconazole oral solution has not been directly compared to other agents in a controlled trial of similar patients.
Esophageal Candidiasis
Table 11: Summary of patient demographics for clinical trials in esophageal candidiasis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (total/efficacy)2 | Mean age (Range)3 | Sex(M/F)3 |
|---|---|---|---|---|---|
| ITR-USA-12 | double-blind, randomized, active- controlled | itraconazole oral solution 100-200 mg o.d. for 3-8 wks1 fluconazole tablet 100-200 mg o.d. | n=63/53 n=63/57 | 38 (24-57) 37 (23-62) | 53/10 55/8 |
- 1. Treatment continued for two weeks beyond resolution of symptoms, but not less than 3 weeks nor more than 8 weeks
- 2. Total: intent-to-treat population; Efficacy: patients included in efficacy analysis
- 3. Values based on total number of study subjects
A double-blind, randomized study (n=110, 102 of whom were HIV-seropositive) compared itraconazole oral solution (100 mg/day) to fluconazole tablets (100 mg/day). The dose of each was increased to 200 mg/day for patients not responding initially. Treatment continued for
2 weeks following a resolution of symptoms for a total duration of 3-8 weeks. Clinical response (a global clinical assessment of cured or improved) was not significantly different between the two study arms and was >90% for both arms. Six of 53 (11%) itraconazole patients and 12 of 57
(21%) fluconazole patients were escalated to the 200 mg dose in this trial. Of the subgroup of patients who responded and entered a follow-up phase (n=88), approximately 23% relapsed across both arms within 4 weeks.
Oral and/or Esophageal Candidiasis
Table 12: Summary of patient demographics for clinical trials in oral and/or esophageal candidiasis
| Study # | Study design | Dosage, route of administration and duration | Study subjects (total/efficacy) 1 | Mean age (Range)2 | Sex (M/F)2 |
|---|---|---|---|---|---|
| ITR-FRA-5 | uncontrolled, open-label | Week 1-2: itraconazole oral solution 100 mg b.i.d. Week 3-4 in case of failure: itraconazole oral solution 200 mg b.i.d. | n=60/40 | 38 (25-69) | 50/10 |
- 1. Total: intent-to-treat population; Efficacy: patients included in efficacy analysis
- 2. Values based on total number of study subjects
An uncontrolled, open-label study (n=40, all patients HIV-seropositive) treated patients clinically unresponsive or refractory to fluconazole tablets (defined as a dose of fluconazole tablets
100-200 mg/day for a minimum of 14 days) with itraconazole oral solution, 100 mg b.i.d. for 14 days. If not cured, itraconazole oral solution treatment was continued at 400 mg b.i.d. for another 14 days. Sixty percent of the evaluable patients had sufficient improvement at week 2; 70% of the patients were clinically cured at the end of treatment period.
15 MICROBIOLOGY
Itraconazole is an orally active triazole antifungal drug which demonstrates antifungal activity on a wide variety of fungi and yeast in vitro.
Itraconazole exhibits in vitro activity against Aspergillus spp., Blastomyces dermatitidis, Cladosporium spp., Coccidioides immitis, Cryptococcus neoformans, Geotrichum spp., Histoplasma spp., including H. capsulatum, Paracoccidioides brasiliensis, Talaromyces marneffei, Sporothrix schenckii and Trichosporon spp., Epidermophyton floccosum, Fonsecaea spp., Malassezia spp., Microsporum spp., Pseudallescheria boydii and Trichophyton spp.
MIC90's for the majority of medically important fungi are between 0.1 and 1.0 mcg/mL, while fungicidal activity is obtained at higher concentrations (10 mcg/mL). The in vitro activity of hydroxy-itraconazole (the only active metabolite) is comparable to the in vitro activity of itraconazole.
For information about the critical minimum inhibitory concentrations established with the EUCAST method for itraconazole please refer to https://www.eucast.org/astoffungi/clinicalbreakpointsforantifungals
In vitro results vary considerably depending on culture medium, inoculum size, conditions of incubation, etc. Because of this variability of in vitro results, most fungi show a higher apparent sensitivity to itraconazole in vivo.
The principal fungus types that are not inhibited by itraconazole are Zygomycetes (e.g., Rhizopus spp., Rhizomucor spp., Mucor spp. and Absidia spp.), Fusarium spp., Scedosporium spp. and Scopulariopsis spp.
Candida krusei, Candida glabrata and Candida guilliermondii are generally the least susceptible
Candida species, with some isolates showing unequivocal resistance to itraconazole in vitro.
The in vivo activity of oral itraconazole observed in experimental animal models of systemic mycoses is shown in Table 13.
Table 13: In vivo activity of oral itraconazole
| Infection | Animal | Delay/ duration 1 (days) | % of animals responding at dosage indicated (mg/kg/day) | Response | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| 1.25 | 2.5 | 5 | 10 | 20 | 40 | 80 | 160 | ||||
| Candidiasis | Guinea pig | 0/14 | 27 | 100 | 96 | 862 | Negative kidney culture | ||||
| Rat | 0/3 | Survived 21 days | |||||||||
| Rabbit | +1/7 | Negative kidney culture | |||||||||
| Aspergillosis | Guinea pig | 0/14 | 83 | 75 | 47 | Survived 28 days | |||||
| Guinea pig | +0/14 | 50 | 83 | Survived 28 days | |||||||
| IC4 guinea pig | 0/28 | 100 | Survived 28 days | ||||||||
| IC4 guinea pig | +1/28 | 80 | Survived 28 days | ||||||||
| Mouse | 0/5 | Negative kidney culture | |||||||||
| Rabbit3 | +3/14 | 100 | Cured | ||||||||
| Cryptococcos is | Guinea pig | +3/35 | 88 | 100 | 732 | 53 | Negative culture (CSF excluded) | ||||
| Mouse | 0/14 | Negative CSF culture | |||||||||
| Rabbit | +4/14 | Negative CSF culture | |||||||||
| Infection | Animal | Delay/ duration 1 (days) | % of animals responding at dosage indicated (mg/kg/day) | Response | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| 1.25 | 2.5 | 5 | 10 | 20 | 40 | 80 | 160 | ||||
| Sporotrichosi s | Guinea pig | 0/28 | 80 | 100 | Cured | ||||||
| Histoplasmos is | Guinea pig | 0/14 | 63 | 100 | Cured | ||||||
| Coccidioidom y- cosis | Rat |
| 1005 | Negative lung culture | |||||||
| Rat | +7/14 | 805 | Negative lung culture | ||||||||
| Paracoccidioi d- omycosis | Mouse | 0/28 | 100 | Survived 28 days | |||||||
- 1. Delay in start of treatment relative to time of infection/duration of treatment.
- 2. 200 mg given to each animal, roughly equivalent to 80 mg/kg/day.
- 3. Itraconazole administered intravenously.
- 4. IC = immunocompromised by cyclophosphamide, corticosteroids or mechlorethamine.
- 5. Actual dosage 16 mg/kg/day.
Resistance and Cross-Resistance
Isolates from several fungal species, (including Aspergillus fumigatus), with decreased susceptibility to itraconazole have been isolated in vitro and from patients receiving prolonged therapy. Azole resistance appears to develop slowly and is often the result of several genetic mutations. Mechanisms that have been described are overexpression of ERG11, which encodes the target enzyme 14α-demethylase, point mutations in ERG11 that lead to decreased target affinity and/or transporter overexpression resulting in increased efflux.
Cross-resistance between members of the azole class has been observed within Candida spp., the finding of cross-resistance is dependent on a number of factors, including the species evaluated, its clinical history, the particular azole compounds compared, and the type of susceptibility test that is performed.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Single-Dose Toxicity
Itraconazole/(HP-β-CD) was administered orally and intravenously to mice, rats and dogs from both genders. The results are summarized in Table 14.
Table 14: Single-dose toxicity studies with itraconazole/(HP-β-CD)
| Species | Route | Sex | LD50-values (mg itraconazole/(HP-β-CD)/kg bwt) |
|---|---|---|---|
| mouse | oral | M & F | > 100/(2500) |
| mouse | intravenous | M & F | > 44.1/(1764) |
| rat | oral | M & F | > 100/(2500) |
|---|---|---|---|
| rat | intravenous | M & F | > 17.6/(704) |
| dog | oral | M & F | > 100/(2500) |
| dog | intravenous | M & F | > 17.6/(704) |
Upon oral administration, all animals survived the maximum dose of 100/(2500) mg/kg body weight (bwt). Clinical responses mainly consisting of soft feces or diarrhea were seen in all three species. As they were also present in the mice and rats dosed with HP-β-CD alone, these phenomena were considered to be due to the osmotic effects of HP-β-CD.
A single intravenous dose of 44.1/(1764) mg/kg bwt in mice and 17.6/(704) mg/kg bwt in rats and dogs did not result in mortality. Clinical effects observed were transient hyperpnea in rats and mice, and dyspnea and loss of righting reflex in dogs. These effects were only seen during the first hours after injection.
Long-Term Toxicity
For the evaluation of repeated oral use of itraconazole/(HP-β-CD), mice, rats and dogs were daily dosed for 3 months. In addition, chronic oral toxicity studies were performed in rats
(6 months) and dogs (12 months). The duration of these studies was done in conformity with the requirements of the major regulatory authorities worldwide.
Table 15: Doses of itraconazole/(HP-β-CD) in studies in mice, rats and dogs
| Study | itraconazole/(HP-β-CD) doses in mg/kg bwt |
|---|---|
| 3 month pilot toxicity in mice | 0/(0), 0/(800), 5/(200), 20/(800), 80/(3200) |
| 3 month toxicity in rats | 0/(0), 0/(4000), 5/(1000), 20/(2000), 80/(4000) |
| 6 month toxicity in rats | 0/(0), 0/(800), 5/(200), 20/(800), 30/(0) |
| 3 (+1)1 month toxicity in dogs | 0/(500), 5/(300), 10/(400), 20/(500) |
| 12 month toxicity in dogs | 0/(0), 0/(800), 5/(200), 20/(800), 20/(0) |
- 1. +1 month of recovery
In the studies performed with itraconazole/(HP-β-CD) in mice, rats and dogs, the itraconazole dose of 5 mg/kg body weight was virtually not toxic. In rats, the only effects observed were, as expected from the toxicological profile of itraconazole, slightly increased serum cholesterol and phospholipid-levels, and minimal histological changes of the adrenal cortex (swelling), but without any cytopathological changes. In dogs, slight histological changes of the mononuclear phagocytosing system (MPS) mainly consisting of an increase in foamy macrophages and adaptive changes in the urinary tract (swelling and vacuolation of epithelial cells in the renal pelvis and the urinary bladder) were the only effects observed, and they were mainly attributable to HP-β-CD.
In mice, dosing at 20/(800) and 80/(3200) mg/kg for 3 months resulted in slight to more pronounced toxicity. Serum aspartate and alanine aminotransferase levels were elevated, and at 80/(3200) mg/kg, associated with histological liver changes (eosinophilic aspect of hepatocytic cytoplasm and increase in individual cell necrosis). Histological examination further revealed modifications of the adrenal cortex (swelling) at 80/(3200) mg/kg bwt. In addition, HP- β-CD-related adaptive changes of the urinary tract were noted at 20/(800) and 80/(3200) mg/kg bwt.
In rats dosed for 3 months, 20/(2000) and 80/(4000) mg/kg bwt were moderately toxic doses. At these doses, target organs or tissues were similar to those observed with itraconazole alone, i.e., the adrenal cortex, the liver, the MPS, and the ovaries. Increased serum cholesterol and phospholipid-levels were also observed. Changes related to the HP-β-CD-vehicle were slightly decreased hematocrit and hemoglobin, a slightly lowered number of red blood cells, and adaptive changes of urinary bladder and renal pelvis.
Dosing in rats for 6 months at 20/(800) mg/kg and at 30/(0) mg/kg, a dose of itraconazole in PEG resulting in a similar systemic exposure, revealed toxicity mainly characterized by some altered blood and serum variables, and histological changes in MPS, liver and adrenal cortex. HP-β-CD-related effects in the 20/(800) and the 0/(800) mg/kg dosed groups were limited to histological changes in urinary tract and to an increased pancreas weight, but without apparent histological changes.
In dogs dosed for 3 months, itraconazole-related toxicity at 10/(400) and 20/(500) mg/kg bwt was confined to a slightly decreased body weight gain, some altered blood and serum variables, a slightly increased adrenal weight and foci of foamy cells in the lungs. The latter finding was also seen in the 0/(500)-vehicle dosed group, indicating that it is at least partially related to HP- β-CD.
Oral administration of HP-β-CD further led to slightly decreased hematocrit and hemoglobin and a slightly lowered number of red blood cells. After 1 month of recovery, the changed parameters in the 0/(500) and 20/(500) mg/kg dosed groups showed good reversibility.
Repeated dosing at 20/(800) or 20/(0) mg/kg for 12 months mainly produced reduced body weight gain and some changed blood and serum variables. At these doses, histological examination revealed itraconazole-related effects on the MPS and the adrenal cortex. Apart from transient softening of the stools and adaptive urinary tract changes, no other HP-β-CD- related effects were present.
Carcinogenicity
Itraconazole was administered in the diet for 23 months to groups of 50 male and 50 female mice and for 24 months to groups of 50 male and 50 female rats in order to evaluate its carcinogenic potential.
In mice, itraconazole showed no evidence of carcinogenicity potential at oral dosage levels up to 80 mg/kg/day (approximately 10x the maximum recommended human dose (MRHD)).
However, female mice receiving 80 mg/kg/day displayed a temporary body weight decrease and an increased incidence of adrenal pigmentation.
Female rats treated with itraconazole at 50 mg/kg/day (6.25xMRHD), had an increased incidence of squamous cell carcinoma of the lung (2/50) as compared to the untreated group. Although the occurrence of squamous cell carcinoma in the lung is extremely uncommon in untreated rats, the increased incidence in this study was not statistically significant. Male rats treated with 25 mg/kg/day (3.1xMRHD) had a slightly increased incidence of soft tissue sarcoma. These sarcoma may have been a consequence of chronic inflammatory reaction of the connective tissue related to a rat-specific response of hypercholesterolemia, which was not observed in dogs or humans.
Genotoxicity
Itraconazole was studied for mutagenic potential by the Salmonella typhimurium microsomal activation (Ames test), Drosophila recessive lethal mutation (Drosophila melanogaster), micronucleus formation (male and female rats), dominant lethal mutation (male and female mice), mouse lymphoma L5178Y test system and chromosome aberration (human lymphocytes). No mutagenic potential was demonstrated with any of these tests.
Reproductive and Developmental Toxicology
Segment I Reproduction Studies
Itraconazole was administered orally by gavage to groups of 24 male and 24 female rats in a segment I study, to assess its effects on male and female fertility. The dose levels studied were 10, 40 and 160 mg/kg/day, which were administered to males (minimum 60 days, prior to mating) and females (14 days prior to mating and a further 8 days during pregnancy). No adverse effects were found in the 10 mg/kg/day groups. There were no effects on fertility in the 40 mg/kg/day groups, but parental toxicity was present.
In the 160 mg/kg/day groups, parental toxicity including deaths occurred (2 males, 16 females). In the few surviving females of the 160 mg/kg/day group, pregnancy rates decreased and resorption rates increased, whereas other fertility parameters such as copulation index, number of corpora lutea, and the number of implantations per pregnant rat were normal. It was concluded that itraconazole had no primary effect on male or female fertility and that any adverse effects on fertility were secondary to the general toxicity seen at a partially lethal level of 160 mg/kg/day. No teratogenic effects were present in this study.
Segment II Reproduction Studies
In rats, itraconazole was administered by gavage (2 studies) and admixed with the diet. The dose levels in all rat studies were 10, 40 and 160 mg/kg/day. In the diet study, where itraconazole was administered to groups of 20 female rats from day 6 through day 15 of pregnancy, maternal toxicity and embryotoxicity were found at 40 and 160 mg/kg/day (100% resorption at 160 mg/kg/day). Teratogenic effects (major skeletal defects or abnormalities secondary to skeletal defects) were present in the offspring of the 40 mg/kg/day females. There were no fetuses of the 160 mg/kg/day dams available.
When itraconazole was administered via gavage to groups of 36 females (from day 8 through day 18 of pregnancy) in one study and groups of approximately 20 females (from day 6 through day 15 of pregnancy) in another study, maternal toxicity, embryotoxicity and teratologic changes were observed at 160 mg/kg/day. The only effect noted in the 40 mg/kg/day group was a slightly lowered pup weight in one of the two studies.
In a segment II rabbit study, the dose levels were 5 (17 females), 20 (15 females) and
80 (16 females) mg/kg/day administered by gavage from day 6 through day 18 of pregnancy. Reduced implantation was found in the 20 mg/kg/day dams but this observation is a predosing effect. In this study no embryotoxicity or teratogenicity was present. A second study was performed with the clinical pellet formulation. Doses administered to groups of 15 female rabbits by gavage were 25, 50 and 100 mg/kg/day from day 6 through day 18 of pregnancy. Slight maternal toxicity was characterized by decreased food consumption during and after dosing of 50 and 100 mg/kg/day. Itraconazole did not produce embryotoxic or teratogenic effects.
Two segment II reproduction studies were also conducted in mice, where itraconazole was administered by gavage from days 6 through 16 of pregnancy. The dose levels were 10, 40 and 160 mg/kg/day in the first study (groups of 24 dosed females) and 40, 80 and 160 mg/kg/day (groups of 30 dosed females) in the second. No adverse effects were found in the dams or fetuses of dams receiving 10 or 40 mg/kg/day. In the 80 and 160 mg/kg/day groups a few malformations (mainly encephaloceles and/or macroglossia) were found. A dose level of
160 mg/kg/day produced both maternal toxicity and embryotoxicity.
In a special segment II teratogenicity study in groups of 10 dosed female rats, it was shown that the embryotoxicity and teratogenicity seen after itraconazole at 160 mg/kg could be reduced by simultaneous administration of arachidonic acid. This protective effect of arachidonic acid is similar to what is known for non-steroidal and steroidal anti-inflammatory drugs. Since itraconazole did not show any relevant in vitro inhibitory activity on the target enzymes of the arachidonic acid pathway, an indirect, adrenal-mediated mechanism was proposed.
To evaluate this hypothesis, adrenalectomy was performed at day 4 of pregnancy in pregnant rats. Adrenalectomy resulted in a reduction of the embryotoxic and teratogenic effects of itraconazole dosed at 40 mg/kg. The data indicate that the adrenal effects seen at high dose levels of itraconazole are, at least partially, responsible for the adverse itraconazole effects on the progeny of pregnant rats.
Segment III Reproduction Studies
Perinatal and postnatal effects were studied in groups of 24 female rats in a segment III study. Itraconazole was administered via gavage at the rates of 5, 20 and 80 mg/kg/day from day 18 of pregnancy through a 3-week lactation period. There were no adverse effects at 5 or
20 mg/kg/day whereas maternal toxicity only was present at the dose level of 80 mg/kg/day.
Except for a marginal effect on pup weight at 80 mg/kg, no embryotoxic or teratogenic or any other adverse effects were noticed in the offspring. In a subsequent, second generation study, no adverse effects on reproduction were noted in rats derived from dams (groups of 10 females) dosed up to 80 mg/kg.
Hydroxypropyl-β-Cyclodextrin (HP-β-CD) – Pharmacology and Toxicology
HP-β-CD is a new carrier molecule designed to enhance oral absorption and exposure to drugs. Chemically, it is a cyclic oligosaccharide built up from 7 glucopyranose units with 4.06 to
5.11 hydroxypropyl groups per molecule of cyclodextrin.
Pharmacology
Pharmacodynamic studies have shown that HP-β-CD has no intrinsic in vivo pharmacological activities that might hinder its presence in the clinical formulation of itraconazole oral solution. No interactions between HP-β-CD and drugs are expected from either a pharmacodynamic or a metabolic point of view.
The oral bioavailability of hydroxypropyl-β-cyclodextrin given as a solubilizer of itraconazole in oral solution is on average lower than 0.5% and is similar to that of hydroxypropyl-β-cyclodextrin alone. This low oral bioavailability of hydroxypropyl-β-cyclodextrin is not modified by the presence of food and is similar after single and repeated administrations.
The pharmacokinetics of HP-β-CD after both intravenous and oral administration are similar in experimental animals and man. Intravenously dosed HP-β-CD is cleared very rapidly from the plasma, mainly by renal excretion of the intact compound. In animals, the tissue distribution is limited, and highest concentrations are measured in the urinary tract. The systemic absorption after oral administration of intact HP-β-CD is low. HP-β-CD is excreted for 50%-62% of the dose as the intact compound in the feces. The bulk of the remaining part is metabolized by the intestinal microflora, and the absorption and tissue distribution of the biodegradation products are limited too. After oral dosing, the gastrointestinal tissues show the highest exposure to intact HP-β-CD as well as its biodegraded products. In view of the limited systemic absorption of
HP-β-CD after oral administration, a stimulant effect on intestinal secretion and motility after high oral doses from 1500 mg/kg bwt onwards can be expected.
Toxicology
Single dose toxicity studies in mice, rats and dogs indicate a wide safety margin after oral and intravenous administration of HP-β-CD. In the (sub)chronic toxicity studies, most effects were of an adaptive nature (histological changes in the urinary tract, softening of feces, activation of the MPS) and showed good reversibility. Slight, reversible liver changes occurred at doses of about 30 times the proposed human dose of HP-β-CD in the itraconazole oral solution.
Oral treatment of juvenile Beagle dogs with HP-β-CD at 1200 mg/kg for a period of up to 13 weeks with a 4-week recovery period was clinically well tolerated with no effects noted when compared to control animals at laboratory or histopathology examination.
Mutagenicity
The chemical structure of HP-β-CD does not raise suspicion for genotoxic activity. Tests on DNA-damage, gene mutations and chromosome aberrations in vitro and in vivo did not reveal any genotoxic activity of HP-β-CD.
Carcinogenicity
In a rat carcinogenicity study, an increased incidence of neoplasms in the large intestine and in the exocrine pancreas was seen. The slightly higher incidence of adenocarcinomas in the large intestine was observed at 5000 mg/kg. The increased incidence was linked to the hypertrophic/ hyperplastic and inflammatory changes in the colonic mucosa brought about by the HP-β-CD- induced increased osmotic forces. There is no evidence of HP-β-CD per se exerting a tumorigenic effect on the large intestine. Hyperplasia and neoplasia of the exocrine pancreas, related to the mitogenic action of CCK, were only seen in those studies where HP-β-CD was given orally to rats. The clinical relevance of these findings is unknown.
In addition, HP-β-CD was found to produce pancreatic exocrine hyperplasia and neoplasia when administered orally to rats at doses of 500, 2000 or 5000 mg/kg/day for 25 months. The likely mechanism is that oral administration of HP-β-CD resulted in a cholecystokinin (CCK)- mediated increase in hyperplasia of the acinar cells in the exocrine pancreas. This rat-specific finding was not observed in the mouse carcinogenicity study at doses 500, 2000 or 5000 mg/kg/day for 22-23 months.
This finding was also not observed in the chronic administration of HP-β-CD for 12 months to dogs (up to 2000 mg/kg bwt with eight dogs in each group) or to female cynomolgus monkeys for 2 years (800/400 mg/kg bwt, 13 monkeys per group) which did not cause hyperplastic/ neoplastic pancreatic changes.
Reproduction and Teratology
HP-β-CD has no antifertile, no direct embryotoxic and no teratogenic effect.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrSPORANOX (itraconazole oral solution 10 mg/mL), Submission Control number: 275526, Product Monograph, Janssen Inc. (October 3, 2023)