


Product Monograph - Carbocaine 1%
Pharmacology
Mepivacaine hydrochloride is 2-piperidinecarboxamide, N-(2,6-dimethylphenyl)-1-methyl, monohydrochloride. It is a white crystalline odorless powder, soluble in water, but very resistant to both acid and alkaline hydrolysis. It has the following structural formula:
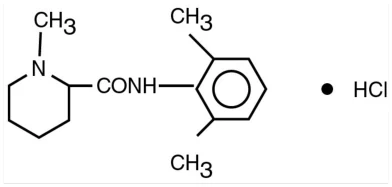
C15H22N2O • HCl
CARBOCAINE contains mepivacaine hydrochloride, an amide local anesthetic, as the active pharmaceutical ingredient. The route of administration for CARBOCAINE is by injection, for local infiltration, peripheral nerve block, and caudal and lumbar epidural blocks. Multiple-dose vials contain methylparaben.
CARBOCAINE (mepivacaine hydrochloride) is a clear and colorless sterile isotonic solution. Each mL of single-dose vial contains 10 mg or 20 mg of mepivacaine hydrochloride (equivalent to 8.71 mg or 17.42 mg of mepivacaine, respectively). Each mL of multiple-dose vial contains 10 mg of mepivacaine hydrochloride (equivalent to 8.71 mg of mepivacaine).
The specific gravity of CARBOCAINE 1% at 25 °C is 1.007 for the single-dose vials and 1.008 for the multiple-dose vials. The specific gravity of CARBOCAINE 1.5% and 2% at 25 °C is 1.008.
Mepivacaine stabilizes the neuronal membrane and prevents the initiation and transmission of nerve impulses, thereby effecting local anesthesia. Its pharmacological properties are somewhat similar to those of lidocaine, which it resembles chemically. Its action is more rapid in onset and somewhat more prolonged than that of lidocaine. It has been employed for all types of infiltration and regional nerve block anesthesia.
Onset of anesthesia is rapid, the time of onset for sensory block ranging from about 3 to 20 minutes depending upon such factors as the anesthetic technique, the type of block, the concentration of the solution and the individual patient. The degree of motor blockade produced is dependent on the concentration of the solution. The 1% concentration will block sensory and sympathetic conduction without loss of motor function and will be effective in small superficial nerve blocks. The 2% concentration of mepivacaine will produce complete sensory and motor block of any nerve group.
The duration of anesthesia also varies depending upon the technique and type of block , the concentration and the individual. Mepivacaine will normally provide anesthesia which is adequate for 2 to 2½ hours of surgery. It has been reported that vasoconstrictors do not significantly prolong anesthesia with CARBOCAINE, but a dilute concentration of epinephrine (1:200,000 or 5 mcg/mL) usually reduces the rate of absorption and plasma concentration of CARBOCAINE.
The drowsiness and lassitude seen with lidocaine have not been commonly noted with mepivacaine. Mepivacaine has shown excellent tissue compatibility: irritation or tissue damage has not been observed.
Pharmacokinetics
Systemic plasma levels of mepivacaine following administration of CARBOCAINE do not correlate with local efficacy.
Mepivacaine is approximately 75% bound to plasma proteins.
Mepivacaine appears to cross the placenta by passive diffusion. The rate and degree of diffusion is governed by (1) the degree of plasma protein binding, (2) the degree of ionization, and (3) the degree of lipid solubility. Fetal/maternal ratios of mepivacaine appear to be inversely related to the degree of plasma protein binding, because only the free, unbound drug is available for placental transfer. The extent of placental transfer is also determined by the degree of ionization and lipid solubility of the drug. Lipid soluble, nonionized drugs readily enter the fetal blood from the maternal circulation. Based on the pharmacokinetic analyses performed in several studies, mepivacaine is rapidly absorbed from the epidural space into the maternal blood stream and readily crosses the placenta as evidenced by detectable mepivacaine blood levels in the fetus as early as 5 minutes after anesthetic block administration. Fetal absorption and distribution of mepivacaine were noted in few cases that demonstrated tissue and organ levels of mepivacaine.
Patients with Hepatic Impairment: Various pharmacokinetic parameters of the local anesthetics including mepivacaine can be significantly altered by the presence of hepatic disease. Patients with hepatic disease, especially those with severe hepatic disease, may be more susceptible to the potential toxicities of the amide-type local anesthetics including mepivacaine.
Patients with Renal Impairment: Various pharmacokinetic parameters of the local anesthetics including mepivacaine can be significantly altered by the presence of renal disease, factors affecting urinary pH, and renal blood flow.
Indications
CARBOCAINE is indicated for production of local or regional analgesia and/or anesthesia by local infiltration, peripheral nerve block techniques, and central neural techniques including epidural and caudal blocks. Specific concentrations and presentations of CARBOCAINE are recommended for each type of block indicated to produce local or regional anesthesia or analgesia.
Contraindications
- Known history of hypersensitivity to mepivacaine or amide-type local anesthetics or to other components of mepivacaine solutions.
- Known history of hypersensitivity to methylparaben and/or propylparaben (preservatives used in multidose solutions), or to their metabolite para amino benzoic acid (PABA).
Warnings
Local anesthetics should only be employed by clinicians who are well versed in diagnosis and management of related toxicity and other acute emergencies which might arise from the block to be employed, and then only after insuring the immediate availability of oxygen, resuscitative drugs, cardiopulmonary resuscitative equipment, and the personnel resources needed for proper management of toxic reactions and related emergencies (see also Adverse Effects and Precautions). Delay in proper management of dose-related toxicity, underventilation from any cause, and/or altered sensitivity may lead to acidosis, cardiac arrest and, possibly death.
An intravenous cannula must be inserted before the local anesthetic is injected for nerve blocks which may result in hypotension or bradycardia, or where acute systemic toxicity may develop following inadvertent intravascular injection.
The lowest dosage of local anesthetic that results in effective anesthesia or analgesia should be used to avoid high plasma levels and serious adverse reactions. Injections should be made slowly or in incremental doses, with frequent aspirations before and during the injection to avoid intravascular injection.
Avoid use of CARBOCAINE solutions containing antimicrobial preservatives, i.e., those supplied in multiple-dose vials, should not be used for epidural or caudal anesthesia, or for any route of administration that would introduce solution into the cerebrospinal fluid because safety has not been established with regard to intrathecal injection, either intentional or accidental such use.
Mepivacaine, when co-administered with epinephrine or other vasopressors, should not be used concomitantly with ergot-type oxytocic drugs, because a severe persistent hypertension may occur. Likewise, solutions of mepivacaine containing a vasoconstrictor, such as epinephrine, should be used with extreme caution in patients receiving monoamine oxidase inhibitors (MAOI) or antidepressants of the triptyline or imipramine types, because severe prolonged hypertension may result.
Local anesthetic procedures should not be used when there is inflammation and/or sepsis in the region of the proposed injection.
There have been reports of lidocaine-induced hypersensitivity reactions leading to Kounis syndrome (acute allergic coronary arteriospasm that can result in myocardial infarction). Kounis syndrome can develop in patients with and without cardiac risk factors, and may present with cardiac and/or allergic symptoms. Given the shared chemical class and mechanism, the risk may be extrapolated, especially in patients with known hypersensitivity to amide anesthetics or a history of allergic cardiovascular events.
These solutions are not intended for spinal anesthesia or dental use.
Precautions
General
Unintended intravascular or intrathecal injection of CARBOCAINE may be associated with systemic toxicities, including CNS or cardiorespiratory depression and coma, progressing ultimately to respiratory arrest. Unintentional intrathecal injection during the intended performance of caudal or lumbar epidural block or nerve blocks near the vertebral column has resulted in underventilation or apnea (“Total or High Spinal”). A high spinal has been characterized by paralysis of the legs, loss of consciousness, respiratory paralysis, and bradycardia.
Aspirate for blood or cerebrospinal fluid (where applicable) before injecting CARBOCAINE, both the initial dose and all subsequent doses, to avoid intravascular or intrathecal injection. However, a negative aspiration for blood or cerebrospinal fluid does not ensure against an intravascular or intrathecal injection.
Use of Test Dose with Epidural Anesthesia
To serve as a warning of unintended intravascular or intrathecal injection, CARBOCAINE without antimicrobial preservative is recommended for use as a test dose with epinephrine prior to administration of the full dose in caudal and lumbar epidural blocks when clinical conditions permit. When using a “continuous” catheter technique, test doses should be given prior to both the initial and all supplemental doses. An effective test dose should contain epinephrine (10 mcg to 15 mcg) to serve as a warning of unintended intravascular injection. The test dose should also contain 45 mg to 50 mg of CARBOCAINE to detect an unintended intrathecal administration. An intravascular or intrathecal injection is still possible even if results of the test dose are negative.
Signs/symptoms of unintended intravascular or intrathecal injection of the test dose of CARBOCAINE with epinephrine and monitoring recommendations are described below.
- Unintended intravascular injection: Likely to produce a transient “epinephrine response” within 45 seconds, consisting of an increase in heart rate and/or systolic blood pressure, circumoral pallor, palpitations, and nervousness in the unsedated patient. The sedated patient may exhibit only a pulse rate increase of 20 or more beats per minute for 15 or more seconds. Therefore, following the test dose, the heart rate should be monitored for increases. Patients on beta-blockers may not manifest changes in heart rate, but blood pressure monitoring can detect a transient rise in systolic blood pressure.
- Unintended intrathecal injection: Evidenced within a few minutes by signs of spinal block (e.g., decreased sensation of the buttocks, paresis of the legs, or, in the sedated patient, absent knee jerk).
The test dose itself may produce a systemic toxic reaction, high spinal or epinephrine-induced cardiovascular effects.
The toxic effects of local anesthetics are additive. If coadministration of other local anesthetics with CARBOCAINE cannot be avoided, monitor patients for neurologic and cardiovascular effects related to local anesthetic systemic toxicity. Mixing any local anesthetic with mepivacaine cannot be recommended because of insufficient data on the clinical use of such mixtures.
Injection of repeated doses of CARBOCAINE may cause significant increases in plasma levels with each repeated dose due to slow accumulation of the drug or its metabolites or to slow metabolic degradation. Tolerance to elevated blood levels varies with the status of the patient. Debilitated, elderly patients, and acutely ill patients should be given reduced doses commensurate with their age and physical status. Local anesthetics should also be used with caution in patients with severe disturbances of cardiac rhythm, shock heart block or hypotension.
Local anesthetic solutions containing a vasoconstrictor should be used cautiously and in carefully restricted quantities in areas of the body supplied by end arteries or having otherwise compromised blood supply such as digits, nose, external ear, penis. Patients with hypertensive vascular disease may exhibit exaggerated vasoconstrictor response. Ischemic injury or necrosis may result.
CARBOCAINE should be used with caution in patients with drug sensitivities. CARBOCAINE is contraindicated in patients with known hypersensitivities to local anesthetics of the amide type, to other components in the formulation, parabens and their metabolite para amino benzoic acid (PABA) (see Contraindications). The use of paraben-containing CARBOCAINE preparations should also be avoided in patients who are allergic to ester local anesthetics.
Use mepivacaine cautiously in patients with hepatic and renal disease. Because amide-type local anesthetics such as mepivacaine are metabolized by the liver and excreted by the kidneys, consider reduced dosing and increased monitoring for mepivacaine systemic toxicity in patients with moderate to severe hepatic and/or renal impairment who are treated with CARBOCAINE, especially with repeat doses.
CARBOCAINE should be given in reduced doses in patients with impaired cardiovascular function (e.g., hypotension, heart block, shock, arrhythmia) because they may be less able to compensate for functional changes associated with the prolongation of AV conduction produced by CARBOCAINE. Monitor patients closely for blood pressure, heart rate, and ECG changes.
Serious dose-related cardiac arrhythmias may occur if preparations containing a vasoconstrictor such as epinephrine are employed in patients during or following the administration of potent inhalation anesthetics. In deciding whether to use these products concurrently in the same patient, the combined action of both agents upon the myocardium, the concentration and volume of vasoconstrictor used, and the time since injection, when applicable, should be taken into account If epinephrine is used, a 1:200 000 concentration is preferred.
Many drugs used during the conduct of anesthesia are considered potential triggering agents for familial malignant hyperthermia. Because it is not known whether amide-type local anesthetics may trigger this reaction and because the need for supplemental general anesthesia cannot be predicted in advance, it is suggested that a standard protocol for management should be available.
Risk of Adverse Reactions with Use in Head and Neck Area
Small doses of local anesthetics (e.g., CARBOCAINE) injected into the head and neck area, including retrobulbar and stellate ganglion blocks, may produce adverse reactions similar to systemic toxicity seen with unintentional intravascular injections of larger doses. Confusion, convulsions, respiratory depression, and/or respiratory arrest, and cardiovascular stimulation or depression have been reported. These reactions may be due to intra-arterial injection of the local anesthetic with retrograde flow to the cerebral circulation. They may also be due to puncture of the dural sheath of the optic nerve during retrobulbar block with diffusion of any local anesthetic along the subdural space to the midbrain. Monitor circulation and respiration and constantly observe patients receiving CARBOCAINE blocks. Resuscitative equipment and drugs, and personnel for treating adverse reactions should be immediately available. The injection procedures require the utmost care. Dosage recommendations should not be exceeded.
Ophthalmologic use
Retrobulbar injections may very occasionally reach the cranial subarachnoid space causing temporary blindness, cardiovascular collapse, apnea, convulsions, etc. These reactions, which may be due to intra-arterial injection or direct injection into the central nervous system via the sheaths of the optic nerve, must be diagnosed and treated promptly.
Retrobulbar and peribulbar injections of local anesthetics carry a low risk of persistent ocular muscle dysfunction. The primary causes include trauma and/or local toxic effects on muscles and/or nerves. The severity of such tissue reactions is related to the degree of trauma, the concentration of the local anesthetic and the duration of exposure of the tissue to the local anesthetic. For this reason, as with all local anesthetics, the lowest effective concentration and dose of local anesthetic should be used. Vasoconstrictors and other additives may aggravate tissue reactions and should be used only when indicated.
Risk of Respiratory Arrest with Use in Ophthalmic Surgery: Clinicians who perform retrobulbar blocks should be aware that there have been reports of respiratory arrest following local anesthetic injection. Prior to retrobulbar block (e.g., with CARBOCAINE), as with all other regional procedures, resuscitative equipment and drugs, and personnel to manage respiratory arrest or depression, convulsions, and cardiac stimulation or depression should be immediately available. As with other anesthetic procedures, patients should be constantly monitored following ophthalmic blocks for signs of these adverse reactions, which may occur following relatively low total doses.
Methemoglobinemia
Cases of methemoglobinemia have been reported in association with local anesthetic use. Although all patients are at risk for methemoglobinemia, patients with glucose-6-phosphate dehydrogenase deficiency, congenital or idiopathic methemoglobinemia, cardiac or pulmonary compromise, infants under 6 months of age, and concurrent exposure to oxidizing agents or their metabolites are more susceptible to developing clinical manifestations of the condition. If local anesthetics must be used in these patients, close monitoring for symptoms and signs of methemoglobinemia is recommended.
Signs of methemoglobinemia may occur immediately or may be delayed some hours after exposure, and are characterized by a cyanotic skin discoloration and/or abnormal coloration of the blood. Methemoglobin levels may continue to rise; therefore, immediate treatment is required to avert more serious CNS and cardiovascular adverse effects, including seizures, coma, arrhythmias, and death. Discontinue CARBOCAINE and any other oxidizing agents. Depending on the severity of the signs and symptoms, patients may respond to supportive care, i.e., oxygen therapy, hydration. A more severe clinical presentation may require treatment with methylene blue, exchange transfusion, or hyperbaric oxygen.
Chondrolysis with Intra-Articular Infusion
Intra-articular infusions of local anesthetics including CARBOCAINE following arthroscopic and other surgical procedures is an unapproved use, and there have been post-marketing reports of chondrolysis in patients receiving such infusions. The majority of reported cases of chondrolysis have involved the shoulder joint; cases of gleno-humeral chondrolysis have been described in pediatric and adult patients following intra-articular infusions of local anesthetics with and without epinephrine for periods of 48 to 72 hours. There is insufficient information to determine whether shorter infusion periods are associated with chondrolysis. The time of onset of symptoms, such as joint pain, stiffness and loss of motion can be variable, but may begin as early as the 2nd month after surgery. Currently, there is no effective treatment for chondrolysis; patients who experienced chondrolysis have required additional diagnostic and therapeutic procedures and some required arthroplasty or shoulder replacement.
Pregnancy Obstetrical anesthesia
Local anesthetics including mepivacaine rapidly cross the placenta, and when used for epidural, paracervical, caudal, or pudendal block anesthesia, can cause varying degrees of maternal, fetal, and neonatal toxicity. The incidence and degree of toxicity depend upon the procedure performed, the type, frequency, and amount of drug used, and the technique of drug administration. Available data for mepivacaine use in pregnant women in early pregnancy are insufficient to establish a drug associated risk of major birth defects or miscarriage. Animal reproduction studies have not been conducted with mepivacaine. Mepivacaine hydrochloride should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Adverse reactions in the parturient, fetus, and neonate involve alterations of the CNS, peripheral vascular tone, and cardiac function. Epidural, paracervical, caudal, or pudendal anesthesia may alter the forces of parturition through changes in uterine contractility or maternal expulsive efforts. Epidural anesthesia has been reported to prolong the second stage of labor by removing the parturient’s reflex urge to bear down or by interfering with motor function. The use of obstetrical anesthesia may increase the need for forceps assistance.
Maternal hypotension has resulted from regional anesthesia. The supine position is dangerous in pregnant women at term because of aortocaval compression by the gravid uterus. Therefore, during treatment of systemic toxicity, maternal hypotension or fetal bradycardia following regional block, the parturient should be maintained in the left lateral decubitus position if possible, or manual displacement of the uterus off the great vessels be accomplished. Elevating the patient’s legs will also help prevent decreases in blood pressure. The recommended maximum dose of the local anesthetic should not be exceeded. Injection should be made slowly and with frequent aspiration. Allow a five-minute interval between sides.
There have been reports of fetal and neonatal deaths associated with administration of mepivacaine for paracervical and/or pudendal nerve blocks in pregnant women during delivery. Adhere to recommended dosages and proper administration techniques for these blocks. There have also been reports of fetal bradycardia, neonatal respiratory depression, and neonatal seizures after maternal administration of mepivacaine during delivery. Inadvertent direct injection into the fetus at delivery with serious outcomes, including death, have been described. The fetal heart rate should be monitored continuously, and electronic fetal monitoring is highly advisable.
Failure to achieve adequate analgesia with recommended doses should arouse suspicion of intravascular or fetal intracranial injection.
The use of some local anesthetic drug products during labor and delivery may be followed by diminished muscle strength and tone for the first day or two of life. The long-term significance of these observations is unknown.
Lactation
There are no available data on the presence of mepivacaine in human milk, the effects on the breastfed infant, or the effect on milk production. Mepivacaine is structurally similar to bupivacaine; available data from case series and a case report demonstrate that bupivacaine is found in human milk at low levels. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for CARBOCAINE and any potential adverse effects on the breastfed child from CARBOCAINE or from the underlying maternal condition.
Hepatic Impairment
Amide-type local anesthetics, such as mepivacaine, are metabolized by the liver. Patients with severe hepatic impairment, because of their inability to metabolize local anesthetics normally, are at a greater risk of developing toxic plasma concentrations, and potentially local anesthetic systemic toxicity. Therefore, consider reduced dosing and increased monitoring for local anesthetic systemic toxicity in patients with moderate to severe hepatic impairment treated with CARBOCAINE, especially with repeat doses.
Renal Impairment
Mepivacaine is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with renal impairment. Therefore, consider reduced dosing and increased monitoring for local anesthetic systemic toxicity in patients with moderate to severe renal impairment treated with CARBOCAINE, especially with repeat doses.
Adverse Reactions
Adverse reactions to CARBOCAINE are characteristic of those associated with other amide-type local anesthetics: A major cause of adverse reactions to this group of drugs is excessive plasma levels, which may be due to overdosage, inadvertent intravascular injection or slow metabolic degradation.
The most commonly encountered acute adverse reactions that demand immediate countermeasures were related to the CNS and the cardiovascular system. These adverse reactions were generally dose-related and due to high plasma levels, which may have resulted from overdosage, rapid absorption from the injection site, diminished tolerance, or from unintentional intravascular injection of the local anesthetic solution. In addition to systemic dose-related toxicity, unintentional intrathecal injection of drug during the intended performance of caudal or lumbar epidural block or nerve blocks near the vertebral column (especially in the head and neck region) has resulted in underventilation or apnea (“Total or High Spinal”). Also, hypotension due to loss of sympathetic tone and respiratory paralysis or underventilation due to cephalad extension of the motor level of anesthesia have occurred. This has led to secondary cardiac arrest when untreated.
Nervous system: Adverse reactions affecting the nervous system were characterized by excitation and/or depression. Disorientation, restlessness, anxiety, dizziness, tinnitus, blurred vision or tremors may occur, possibly proceeding to convulsions. However, excitement may be transient or absent, with depression being the first manifestation of an adverse reaction. This may quickly be followed by drowsiness merging into unconsciousness and respiratory arrest Other CNS effects may be nausea, vomiting, chills and constriction of the pupils.
Neurologic effects following epidural or caudal anesthesia have included spinal block of varying magnitude (including high or total spinal block); hypotension secondary to spinal block; urinary retention; fecal and urinary incontinence; loss of perineal sensation and sexual function; persistent anesthesia, paresthesia, weakness, paralysis of the lower extremities and loss of sphincter control, all of which may have slow, incomplete or no recovery; headache; backache; septic meningitis; meningismus, slowing of labor; increased incidence of forceps delivery; cranial nerve palsies due to traction on nerves from loss of cerebrospinal fluid.
In the practice of caudal or lumbar epidural block, unintentional penetration of the subarachnoid space by the catheter or needle has occurred. Subsequent adverse effects may have depended partially on the amount of drug administered intrathecally and the physiological and physical effects of a dural puncture. A high spinal has been characterized by paralysis of the legs, loss of consciousness, respiratory paralysis, and bradycardia.
Neurologic effects following other procedures or routes of administration have included persistent anesthesia, paresthesia, weakness, paralysis, all with slow, incomplete, or no recovery.
The incidence of convulsions varied with the procedure used and the total dose administered. In a survey of studies of epidural anesthesia, overt toxicity progressing to convulsions occurred in approximately 0.1% of local anesthetic administrations. The incidences of adverse neurologic reactions associated with the use of local anesthetics may be related to the total dose of local anesthetic administered and are also dependent upon the particular drug used, the route of administration, and the physical status of the patient.
Cardiovascular: High doses or unintentional intravascular injection have led to high plasma levels and related depression of the myocardium, decreased cardiac output, heart block hypotension (or sometimes hypertension) bradycardia, ventricular arrhythmias and possibly cardiac arrest.
Immune system: Allergic-type reactions are rare and have occurred as a result of sensitivity to mepivacaine or to other formulation ingredients, such as the antimicrobial preservative methylparaben, contained in multiple-dose vials. Cross-sensitivity among members of amide-type local anesthetic group has been reported.
Overdose
Symptoms and Treatment: Acute emergencies from use of CARBOCAINE are generally related to high plasma levels encountered during therapeutic use or to unintended intrathecal injection (see Precautions and Adverse Reactions). If not treated immediately, convulsions with simultaneous hypoxia, hypercarbia, and acidosis, plus myocardial depression from the direct effects of mepivacaine may result in cardiac arrhythmias, bradycardia, asystole, ventricular fibrillation, or cardiac arrest. Respiratory abnormalities, including apnea, may occur. Hypoventilation or apnea due to unintentional intrathecal injection of CARBOCAINE may produce these same signs and also lead to cardiac arrest if ventilatory support is not instituted. If cardiac arrest should occur, successful outcome may require prolonged resuscitative efforts.
Toxic effects of local anesthetics require symptomatic treatment there is no specific cure. The physician should be prepared to maintain an airway and to support ventilation with oxygen and assisted or controlled respiration as required. Supportive treatment of circulatory depression may require Advanced Cardiac Life Support measures.
Convulsions may be controlled with oxygen and i.v. administration, in small increments, of a barbiturate or muscle relaxant, as follows: preferably, an ultra short-acting barbiturate such as thiopental or thiamylal: if this is not available, a short-acting barbiturate (e.g. secobarbital or pentobarbital) or a short-acting muscle relaxant (succinylcholine). I.V. muscle relaxants and barbiturates should only be administered by those familiar with their use.
Dosage
The dosage of CARBOCAINE administered varies with the anesthetic procedure, the area to be anesthetized, the vascularity of the tissues, the number of neuronal segments to be blocked, the depth of anesthesia and degree of muscle relaxation required, the duration of anesthesia desired, individual tolerance and the physical condition of the patient. The recommended single adult dose for unsedated, healthy, normal-sized individuals should not usually exceed 400 mg. The following dosages have generally proved satisfactory and are therefore suggested as a guide. Administer the smallest dosage and concentration required to produce the desired result. The recommended dosage is based on requirements for the average adult.
Table 1. Recommended Concentrations and Doses of CARBOCAINE for Adults
| Procedure | Concentration | Total Dose | |
| mL | mg | ||
| Cervical, brachial, intercostal nerve block | 1% (10 mg/mL) | 5 mL to 40 mL | 50 mg to 400 mg |
2% (20 mg/mL) | 5 mL to 20 mL | 100 mg to 400 mg | |
| Pudendal nerve block | 1% (10 mg/mL) | 2.5 mL to 20 mL administered on each side | 25 mg to 200 mg administered on each side |
2% (20 mg/mL) | 2.5 mL to 10 mL administered on each side | 50 mg to 200 mg administered on each side | |
Transvaginal block (paracervical plus pudendal) | 1% (10 mg/mL) | up to 15 mL administered on each side | up to 150 mg administered on each side |
| Paracervical blocka | 1% (10 mg/mL) | up to 10 mL administered on each side | up to 100 mg administered on each side |
| Caudal and epidural blockb | 1% (10 mg/mL) | 15 mL to 30 mL | 150 mg to 300 mg |
2% (20 mg/mL) | 10 mL to 20 mL | 200 mg to 400 mg | |
| Infiltrationc | 1% (10 mg/mL) | up to 40 mL | up to 400 mg |
Therapeutic block (pain management) | 1% (10 mg/mL) | 1 mL to 5 mL | 10 mg to 50 mg |
2% (20 mg/mL) | 1 mL to 5 mL | 20 mg to 100 mg | |
a This is the maximum recommended dose per 90-minute period in obstetrical and non-obstetrical patients. Inject slowly, 5 minutes between sides.
b Use only single-dose vials which do not contain a preservative.
Pediatrics: The pediatric dose should be carefully based on weight in pediatric patients (not exceeding 5 to 6 mg/kg), especially those weighing less than 13.6 kg. In children under 3 years of age or weighing less than 13.6 kg, 1% solutions should be employed.
Hepatic Impairment: Mepivacaine is metabolized primarily by the liver. Therefore, consider reduced dosing and increased monitoring for local anesthetic systemic toxicity in patients with moderate to severe hepatic impairment, especially with repeat doses.
Renal Impairment: Mepivacaine and mepivacaine metabolites are known to be substantially excreted by the kidney. Therefore, consider reduced dosing and increased monitoring for local anesthetic systemic toxicity in patients with moderate to severe renal impairment, especially with repeat doses.
Geriatrics: Because elderly patients are more likely to have decreased hepatic and/or renal function, care should be taken in dose selection, and it may be useful to monitor hepatic and/or renal function.
Mepivacaine solution may be diluted with an equal part of sodium chloride injection USP. Dosages in excess of the aforementioned amounts have been administered without serious side effects. Do not exceed a total daily dosage of 1,000 mg in 24 hours because of slow accumulation of the anesthetic or its derivatives or slower than normal metabolic degradation or detoxification with repeat administration. While maximum doses of 7 mg/kg (550 mg) have been administered in some patients, these are not recommended, except in exceptional circumstances. Under no circumstances should administration be repeated at intervals less than 1.5 hours.
Use in Epidural Anesthesia: During the administration of epidural anesthesia, it is recommended that a test dose of CARBOCAINE without antimicrobial preservative be administered initially and the effects monitored before the full dose is given. When using a “continuous” catheter technique, test doses should be given prior to both the initial and all supplemental doses.
During epidural administration, administer CARBOCAINE solutions in incremental doses with sufficient time between doses to detect toxic manifestations of unintentional intravascular or intrathecal injection. Administer injections slowly, with frequent aspirations before and during the injection to avoid intravascular injection. Perform syringe aspirations before and during each supplemental injection in continuous (intermittent) catheter techniques. Repeat doses should be preceded by a test dose containing epinephrine if not clinically contraindicated. Use only the single-dose vials for caudal or epidural anesthesia; avoid use of the multiple-dose vials for these procedures, which contain a preservative (see Precautions).
Test Dose for Caudal and Lumbar Epidural Blocks: CARBOCAINE without antimicrobial preservative is recommended for use as a test dose with epinephrine prior to caudal and lumbar epidural blocks when clinical conditions permit. An effective test dose should contain epinephrine (10 mcg to 15 mcg) to serve as a warning of unintended intravascular injection. The test dose should also contain 45 mg to 50 mg of CARBOCAINE to detect an unintended intrathecal administration. When using a “continuous” catheter technique, test doses should be given prior to both the original and all reinforcing doses, because plastic tubing in the epidural space can migrate into a blood vessel or through the dura. Closely monitor for early clinical signs of toxicity following each test dose (see Precautions). Allot adequate time for onset of spinal block to detect possible intrathecal injection. An intravascular or intrathecal injection is still possible even if results of the test dose are negative. The test dose itself may produce a systemic toxic reaction, high spinal, or cardiovascular effects from the epinephrine (see Precautions, Overdosage).
Supplied: Infiltration and Nerve block: Each mL of solution contains: mepivacaine HCl 10 mg in water for injection. Nonmedicinal ingredients: sodium chloride and methylparaben. May also contain sodium hydroxide and/or hydrochloric acid (for pH adjustment). Gluten-, lactose- and sulfite-free; Multiple dose vials of 50 mL (1%), boxes of 5.
Caudal and Epidural block: Each ml of solution contains: mepivacaine HCI 10 mg in water for injection. Nonmedicinal ingredients: calcium chloride (dihydrate), potassium chloride and sodium chloride. May also contain sodium hydroxide and/or hydrochloric acid (for pH adjustment). Gluten-, lactose-, preservative- and sulfite-free. Single dose vials of 30 mL (1%), boxes of 5.
Caudal and Epidural block: Each ml of solution contains: mepivacaine HCI 20 mg in water for injection. Nonmedicinal ingredients: calcium chloride (dihydrate), potassium chloride and sodium chloride. May also contain sodium hydroxide and/or hydrochloric acid (for pH adjustment). Gluten-, lactose-, preservative- and sulfite-free. Single dose vials of 20 mL (2%), boxes of 5.
Store at 20 °C to 25 °C.