


Product Monograph - Instillagel
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Urethral | Single Use Plastic Syringe (6 mL and 11 mL) / Lidocaine HCl 2% w/w and Chlorhexidine Gluconate 0.05% w/w | Methylparaben, Propylparaben, Hydroxyethylcellulose, Sodium Hydroxide, Propylene Glycol, Purified Water |
INDICATIONS AND CLINICAL USE
Instillagel is indicated for surface anaesthesia, lubrication and antisepsis for:
- The male and female urethra during cystoscopy
- Catheterization
- Exploration by sound and other endourethral operations
Instillagel clinical use has been reported extensively in the published literature. Since the early 1970’s, a large number of published studies have demonstrated both the analgesic and antimicrobial efficacy of Instillagel in urethral procedures. In total, more than 1000 patients were exposed to Instillagel in 10 separate clinical trials, and exposure of more than 22 000 patients to Instillagel were described in literature references. To date, over 350 million applications of Instillagel in over 34 countries worldwide, have resulted in few adverse events (see ADVERSE REACTIONS). This body of data confirms that this product is well tolerated and is effective for its intended purpose.
CONTRAINDICATIONS
- Patients under 2 years of age.
- Known or suspected hypersensitivity to local anesthetics of the amide type, to chlorhexidine or to any ingredient in the formulation (e.g. methylparaben, propylparaben etc.) (see DOSAGE FORMS, COMPOSITION AND PACKAGING section).
WARNINGS AND PRECAUTIONS
Serious Warnings and Precautions
|
General
EXCESSIVE DOSAGE, OR SHORT INTERVALS BETWEEN DOSES, CAN RESULT IN HIGH PLASMA LEVELS OF LIDOCAINE OR ITS METABOLITES AND SERIOUS ADVERSE EFFECTS. Absorption from the mucous membranes is variable but is especially high from the bronchial tree. Such applications may therefore result in rapidly rising or excessive plasma concentrations, with an increased risk for toxic symptoms, such as convulsions. PATIENTS SHOULD BE INSTRUCTED TO STRICTLY ADHERE TO THE RECOMMENDED DOSAGE. This is especially important in children where doses vary with weight. The management of serious adverse reactions may require the use of resuscitative equipment, oxygen and other resuscitative drugs (see OVERDOSAGE).
Instillagel should be used with caution in patients with sepsis and/or traumatized mucosa at the area of application, since under such conditions there is the potential for rapid systemic absorption.
The lowest dosage that results in effective anaesthesia should be used to avoid high plasma levels and serious adverse effects. Tolerance to elevated blood levels varies with the status of the patient. Debilitated, elderly patients, acutely ill patients, and children should be given reduced doses commensurate with their age and physical condition.
Instillagel should also be used with caution in patients with epilepsy, impaired cardiac conduction, bradycardia, impaired hepatic or renal function and in severe shock.
Instillagel must not be used in children under the age of 2 as there is insufficient data to support the safety and efficacy of this product in this patient population at this time (see CONTRAINDICATIONS).
Avoid contact with eyes.
Many drugs used during the conduct of anaesthesia are considered potential triggering agents for familial malignant hyperthermia. It has been shown that the use of amide local anesthetics in malignant hyperthermia patients is safe. However, the development of malignant hyperthermia during surgery may not be prevented by neural blockade. It is also difficult to predict the need for supplemental general anaesthesia. Therefore, a standard protocol for the management of malignant hyperthermia should be available.
Carcinogenesis and Mutagenesis
Genotoxicity tests with lidocaine showed no evidence of mutagenic potential. A metabolite of lidocaine, 2,6-xylidine, showed weak evidence of activity in some genotoxicity tests. A chronic oral toxicity study of the metabolite 2,6-xylidine (0, 14, 45, 135 mg/kg) administered in feed to rats showed that there was a significantly greater incidence of nasal cavity tumors in male and female animals that had daily oral exposure to the highest dose of 2,6-xylidine for 2 years. The lowest tumor-inducing dose tested in animals (135 mg/kg) corresponds to approximately 60 times the amount of 2,6-xylidine to which a 50 kg subject would be exposed following the application of 22 mL of lidocaine jelly 2% for 24 hours on the mucosa, assuming an extent of absorption of 100% and 80% conversion to 2,6 xylidine. Based on a yearly exposure (once daily dosing with 2,6-xylidine in animals and 5 treatment sessions with 22 mL lidocaine jelly 2% in humans), the safety margins would be approximately 3200 times when comparing the exposure in animals to man.
Cardiovascular
Instillagel should be used with caution in patients with impaired cardiovascular function since they may be less able to compensate for functional changes associated with the prolongation of A-V conduction produced by amide-type local anesthetics.
Lidocaine should be used with caution in patients in severe shock.
Ear/Nose/Throat
Avoid contact of Instillagel with the middle ear.
Genitourinary
In the presence of severe damage to the urethra, an excessive hypotensive response may occur.
Hepatic
Because amide-type local anesthetics such as lidocaine are metabolized by the liver, these drugs, especially repeated doses, should be used cautiously in patients with hepatic disease. Patients with severe hepatic disease, because of their inability to metabolize local anesthetics normally, are at greater risk of developing toxic plasma concentrations.
Neurologic
Avoid contact with brain and meninges. Products containing local anesthetics should be used with caution in epileptics.
Epilepsy: The risk of central nervous system side effects when using lidocaine in patients with epilepsy is very low, provided that the dose recommendations are followed. (See DOSAGE AND ADMINISTRATION).
Locomotion and Coordination: Topical lidocaine formulations generally result in low plasma concentrations because of a low degree of systemic absorption. However, in the case of high plasma concentrations, local anesthetics may have a very mild effect on mental function and may temporarily impair locomotion and coordination.
Renal
Lidocaine should be used with caution in patients with severely impaired renal function. Only a small fraction (2%) of lidocaine is excreted unchanged in the urine. Lidocaine is metabolized primarily by the liver to monoethylglycinexylidine (MEGX, which has some CNS activity), and then further to the inactive metabolites glycinexylidine (GX) and 2,6-xylidine (see ACTION AND CLINICAL PHARMACOLOGY). Renal impairment is not expected to significantly affect the pharmacokinetics of lidocaine when Instillagel is used according to dosage instructions (see DOSAGE AND ADMINISTRATION).
Sensitivity/Resistance
Instillagel should be used with caution in persons with known drug sensitivities. Patients allergic to para-aminobenzoic acid derivatives (procaine, tetracaine, benzocaine, etc.) have not shown cross-sensitivity to lidocaine.
Special Populations
Debilitated patients, acutely ill patients, and patients with sepsis should be given reduced doses commensurate with their age, weight and physical condition because they may be more sensitive to systemic effects due to increased blood levels of lidocaine following repeated doses.
Pregnant Women: There are no adequate and well-controlled studies in pregnant women on the effect of lidocaine on the developing fetus.
Lidocaine readily crosses the placenta. During the first 3 months of pregnancy Instillagel should be used only if absolutely necessary.
It is reasonable to assume that a large number of pregnant women and women of childbearing age have been given lidocaine. No specific disturbances to the reproductive process have so far been reported, e.g., no increased incidence of malformations. However, care should be given during early pregnancy when maximum organogenesis takes place.
It is not known whether chlorhexidine gluconate crosses the placenta.
Labour and Delivery: Lidocaine and chlorhexidine are not contraindicated in labour and delivery. Should Instillagel be used concomitantly with other products containing lidocaine and/or chlorhexidine, the total dose contributed by all formulations must be kept in mind.
Nursing Women: Lidocaine and its metabolites are excreted in the breast milk. At therapeutic doses, the quantities of lidocaine and its metabolites in breast milk are small and generally are not expected to be a risk for the infant.
It is not known whether chlorhexidine gluconate is distributed into milk.
Pediatrics: Children should be given reduced doses commensurate with their age, weight and physical condition because they may be more sensitive to systemic effects due to increased blood levels of lidocaine following repeated doses (see DOSAGE AND ADMINISTRATION).
Instillagel must not be used in children under the age of 2 as there is insufficient data to support the safety and efficacy of this product in this patient population at this time (see CONTRAINDICATIONS).
Geriatrics: Elderly patients may be more sensitive to systemic effects due to increased blood levels of lidocaine following repeated doses and may require dose reductions.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Lidocaine
Adverse experiences following the administration of lidocaine are similar in nature to those observed with other amide local anesthetic agents. These adverse experiences are, in general, dose-related and may result from high plasma levels caused by overdosage or rapid absorption, or may result from a hypersensitivity, idiosyncrasy or diminished tolerance on the part of the patient.
Serious adverse experiences are generally systemic in nature. The following types are those most commonly reported:
Central Nervous System: CNS manifestations are excitatory and/or depressant and may be characterized by circumoral paresthesia, light-headedness, nervousness, apprehension, euphoria, confusion, dizziness, drowsiness, hyperacusis, tinnitus, blurred vision, vomiting, sensations of heat, cold or numbness, twitching, tremors, convulsions, unconsciousness, respiratory depression and arrest. The excitatory manifestations may be very brief or may not occur at all, in which case the first manifestation of toxicity may be drowsiness merging into unconsciousness and respiratory arrest.
Drowsiness following the administration of lidocaine is usually an early sign of a high lidocaine plasma level and may occur as a consequence of rapid absorption.
Cardiovascular: Cardiovascular manifestations are usually depressant and are characterized by bradycardia, hypotension, arrhythmia and cardiovascular collapse, which may lead to cardiac arrest.
Allergic: Allergic reactions are characterized by cutaneous lesions, urticaria, oedema or, in the most severe instances, anaphylactic shock. Allergic reactions of the amide type are rare and may occur as a result of sensitivity either to the local anesthetic agent or to other components in the formulation.
Chlorhexidine
Irritative skin reactions can occasionally occur. Generalized allergic reactions to chlorhexidine have also been reported but are extremely rare.
Post-Marketing Experience
Instillagel has been available in Europe for over 30 years and is marketed in over 34 countries. Of the 350 million applications of Instillagel, 59 spontaneous adverse drug reactions have been reported to the manufacturer. Of these, 9 were anaphylactic reactions, 3 were allergic reactions and 10 were local discomfort.
DRUG INTERACTIONS
Overview
Lidocaine is mainly metabolized in the liver by CYP1A2 and CYP3A4 and has a high hepatic extraction ratio. The hepatic clearance of lidocaine is therefore expected to depend largely on blood flow.
Two strong inhibitors of CYP3A4, erythromycin and itraconazole, had no effect on the pharmacokinetics of intravenous lidocaine. Strong inhibitors of CYP1A2, such as fluvoxamine, given concomitantly with lidocaine can cause a metabolic interaction leading to an increased lidocaine plasma concentration.
Prolonged administration of lidocaine should therefore be avoided in patients treated with strong inhibitors of CYP1A2 such as fluvoxamine. This effect is not expected to be relevant after the short application times of urethral lidocaine products. Propranolol and cimetidine have been reported to reduce intravenous lidocaine clearance similarly to strong inhibitors of CYP3A4, but this is not considered clinically significant for urethral use.
With the low systemic exposure and short duration of urethral application, metabolic drug-drug interactions of clinical significance with lidocaine are unlikely. Clinically relevant pharmacodynamic drug interactions may occur with other local anesthetics or structurally related drugs, and Class I and Class III antiarrhythmic drugs due to additive effects.
Drug-Drug Interactions
Local Anesthetics and Agents Structurally Related to Amide-Type Local Anesthetics
Instillagel should be used with caution in patients receiving other local anesthetics or agents structurally related to amide-type local anesthetics (e.g. antiarrhythmics such as mexiletine), since the toxic effects are additive.
Antiarrhythmic Drugs
Class I Antiarrhythmic Drugs
Class I antiarrhythmic drugs (such as mexiletine) should be used with caution since toxic effects are additive and potentially synergistic.
Class III Antiarrhythmic Drugs
Caution is advised when using Class III antiarrhythmic drugs concomitantly with lidocaine due to potential pharmacodynamic or pharmacokinetic interactions with lidocaine, or both. A drug interaction study has shown that the plasma concentration of lidocaine may be increased following administration of a therapeutic dose of intravenous lidocaine to patients treated with amiodarone (n=6). Case reports have described toxicity in patients treated concomitantly with lidocaine and amiodarone. Patients treated with Class III antiarrhythmic drugs (e.g. amiodarone) should be kept under close surveillance and ECG monitoring should be considered, since cardiac effects of these drugs and lidocaine may be additive.
β-blockers: Propranolol has been reported to reduce intravenous lidocaine clearance up to 47%, probably by reduced liver blood flow and/or inhibition of microsomal liver enzymes. This effect is less than that reported for strong inhibitors of CYP1A2 but of the same order as that of strong inhibitors of CYP3A4. However, a clinically relevant interaction with propranolol only needs to be considered during long-term treatment.
Strong Inhibitors of CYP1A2 and CYP3A4: Cytochrome CYP1A2 and CYP3A4 are involved in the formation of MEGX.
Fluvoxamine: In vivo the plasma clearance of intravenous lidocaine was reduced by 41 to 60% during coadministration of fluvoxamine, a selective and potent CYP1A2 inhibitor. Strong inhibitors of CYP1A2, such as fluvoxamine, given during prolonged administration of lidocaine to areas with high extent of systemic absorption can cause a metabolic interaction leading to an increased lidocaine plasma concentration.
Erythromycin and Itraconazole: Erythromycin and Itraconazole, strong inhibitors of CYP3A4, have shown a modest reduction in lidocaine clearance, 9 to 18%. During combined coadministration with fluvoxamine and erythromycin the plasma clearance of lidocaine was reduced by 53%.
Drug-Food Interactions
Interactions of lidocaine and chlorhexidine with food have not been established.
Drug-Herb Interactions
Interactions of lidocaine and chlorhexidine with herbal products have not been established.
Drug-Laboratory Tests Interactions
Interactions of lidocaine and chlorhexidine with laboratory tests have not been established.
Drug-Lifestyle Interactions
Interactions of lidocaine and chlorhexidine with lifestyle have not been established.
DOSAGE AND ADMINISTRATION
Dosing Considerations
When used concomitantly with other products containing lidocaine, the total lidocaine dose contributed by all formulations must be kept in mind.
Special Populations
Lidocaine should also be used with caution in patients with epilepsy, impaired cardiac conduction, bradycardia, impaired hepatic or renal function and in severe shock (see WARNINGS AND PRECAUTIONS).
Debilitated patients, elderly patients, acutely ill patients, patients with sepsis, and children should be given reduced doses commensurate with their age, weight and physical condition (see WARNINGS AND PRECAUTIONS).
Instillagel must not be used in children under the age of 2 as there is insufficient data to support the safety and efficacy of this product in this patient population at this time (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS).
Recommended Dose and Dosage Adjustment
Urethral anaesthesia, lubrication and antiseptic action
Male Adult Urethra: Instil 11 mL, and possibly an additional 6 or 11 mL. The entire urethral area, including the external sphincter must be covered with the lubricating film and anaesthetized for germ-free and painless introduction of instruments. A penile clamp is attached in the region of the sulcus coronarius.
When anaesthesia is especially important, e.g., during sounding or cystoscopy, a larger quantity of gel (e.g., 28 to 39 mL) may be instilled in 3 to 4 portions and allowed to act for 10 to 12 minutes before insertion of the instrument. A 28 mL dose may be achieved by using the contents of two 11 mL syringes and one 6 mL syringe; a 39 mL dose may be achieved by using the contents of three 11 mL syringes and one 6 mL syringe. The gel instilled into the bladder at these doses is also effective for procedures in this region.
To anaesthetize, lubricate and provide antisepsis of only the anterior male urethra, e.g., for catheterization, instil 6 or 11 mL. After the normal cleaning of the glans and the external urethral orifice, instil Instillagel slowly into the urethra, keeping the glans compressed, until the local anesthetic and antiseptic action has set in.
Female Adult Urethra: Instil 6 mL of gel in small portions to fill the whole urethra. If desired, some gel may be deposited on the orifice and covered with a cotton swab.
In order to obtain adequate anaesthesia and antiseptic action, 5-10 minutes should be allowed prior to performing urological procedures.
Maximum Dosage: Adults: No more than 4 doses should be given during a 24-hour period.
Children (2 to 12 years): It is difficult to recommend a maximum dose of any drug for children since this varies as a function of age and weight. The maximum amount of lidocaine per dose should not exceed 6 mg/kg of body weight or 3 mL per 10 kg weight. No more than 4 doses should be given during a 24-hour period.
For children over 12 years of age doses should be commensurate with weight and physical condition.
OVERDOSAGE
Acute systemic toxicity from local anesthetics is generally related to high plasma levels encountered during therapeutic use of local anesthetics and originates mainly in the central nervous and the cardiovascular systems (see ADVERSE REACTIONS, WARNINGS AND PRECAUTIONS).
Limited information is available on the acute toxicity of chlorhexidine gluconate following inadvertent ingestion of the drug. Acute effects of accidental ingestion of chlorhexidine gluconate generally are associated only with high doses; if a small amount of the drug is swallowed, adverse effects are unlikely.
Symptoms: CNS toxicity is a graded response, with symptoms and signs of escalating severity. The first symptoms are circumoral paresthesia, numbness of the tongue, light-headedness, hyperacusis and tinnitus. Visual disturbance and muscular tremors are more serious and precede the onset of generalized convulsions. Unconsciousness and grand mal convulsions may follow, which may last from a few seconds to several minutes. Hypoxia and hypercarbia occur rapidly following convulsions due to the increased muscular activity, together with the interference with normal respiration. In severe cases apnea may occur. Acidosis increases the toxic effects of local anesthetics.
Recovery is due to redistribution and metabolism of the local anesthetic drug. Recovery may be rapid unless large amounts of the drug have been administered.
Cardiovascular effects may be seen in cases with high systemic concentrations. Severe hypotension, bradycardia, arrhythmia and cardiovascular collapse may be the result in such cases.
Cardiovascular toxic effects are generally preceded by signs of toxicity in the CNS, unless the patient is receiving a general anesthetic or is heavily sedated with drugs such as a benzodiazepine or barbiturate.
Treatment: The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient's state of consciousness after each local anesthetic administration. At the first sign of change, oxygen should be administered.
The first step in the management of systemic toxic reactions consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. This may prevent convulsions if they have not already occurred.
If convulsions occur, the objective of the treatment is to maintain ventilation and oxygenation and support circulation. Oxygen must be given, and ventilation assisted if necessary (mask and bag or tracheal intubation). Should convulsions not stop spontaneously after 15-20 seconds, an anticonvulsant should be given iv to facilitate adequate ventilation and oxygenation. Thiopental sodium 1-3 mg/kg iv is the first choice. Alternatively, diazepam 0.1 mg/kg bw iv may be used, although its action will be slow. Prolonged convulsions may jeopardise the patient's ventilation and oxygenation. If so, injection of a muscle relaxant (e.g. succinylcholine 1 mg/kg bw) will facilitate ventilation, and oxygenation can be controlled. Early endotracheal intubation is required when succinylcholine is used to control motor seizure activity.
If cardiovascular depression is evident (hypotension, bradycardia), ephedrine 5 to 10 mg i.v. should be given and may be repeated, if necessary, after 2 to 3 minutes.
Should circulatory arrest occur, immediate cardiopulmonary resuscitation should be instituted. Optimal oxygenation and ventilation and circulatory support as well as treatment of acidosis are of vital importance, since hypoxia and acidosis will increase the systemic toxicity of local anesthetics. Epinephrine (0.1 to 0.2 mg as i.v. or intracardial injections) should be given as soon as possible and repeated, if necessary.
Children should be given doses commensurate with their age and weight.
If taken orally, treat with gastric lavage using milk, raw egg, gelatin or mild soap. Employ supportive measures as appropriate (see above).
Accidental i.v. infusion: Blood transfusion may be necessary to counteract hemolysis.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
|---|
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Lidocaine
Lidocaine stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses, thereby effecting local anesthetic action. Local anesthetics of the amide type are thought to act within the sodium channels of the nerve membrane.
Onset of Action: Anaesthesia is achieved within 5 minutes, depending on the area of application. Duration of anaesthesia is approximately 20 to 30 minutes. Lidocaine is ineffective when applied to intact skin.
Hemodynamics: Lidocaine, like other local anesthetics, may also have effects on excitable membranes in the brain and myocardium. If excessive amounts of drug reach systemic circulation rapidly, symptoms and signs of toxicity will appear, emanating from the central nervous and cardiovascular systems.
CNS toxicity (see OVERDOSAGE) usually precedes the cardiovascular effects since it occurs at lower plasma concentrations. Direct effects of local anesthetics on the heart include slow conduction, negative inotropism and eventually cardiac arrest.
Chlorhexidine
Chlorhexidine is effective against a wide range of gram-negative and gram-positive vegetative bacteria, yeasts, dermatophyte fungi and lipophilic viruses. It is inactive against bacterial spores except at elevated temperatures.
Because of its cationic nature, chlorhexidine binds strongly to skin, mucosa and other tissues and is thus very poorly absorbed. No detectable blood levels have been found in man following oral use. Percutaneous absorption, if it occurs at all, is insignificant.
The antiseptic action of chlorhexidine gluconate is such that the microbial organisms normally present in the distal region of the urethra are killed within 5-10 min. Ascent of microbial microorganisms following urological interventions, or their upward displacement, is thereby largely prevented.
Pharmacokinetics of Lidocaine
Absorption: The rate and extent of absorption depends upon concentration and total dose administered, the specific site of application and duration of exposure. In general, the rate of absorption of local anesthetic agents following topical application to wound surfaces and mucous membranes is high, and occurs most rapidly after intratracheal and bronchial administration. The absorption of lidocaine jelly from the nasopharynx is usually lower than with other lidocaine products. Blood concentrations of lidocaine after instillation of the jelly in the intact urethra and bladder in doses up to 800 mg are fairly low and below toxic levels. Lidocaine is also well absorbed from the gastrointestinal tract, although little intact drug may appear in the circulation because of biotransformation in the liver.
Distribution: Lidocaine has a total plasma clearance of 0.95 L/min and a volume of distribution at steady state of 91 L.
Lidocaine readily crosses the placenta, and equilibrium in regard to free, unbound drug will be reached. Because the degree of plasma protein binding in the fetus is less than in the mother, the total plasma concentration will be greater in the mother, but the free concentrations will be the same.
Normally about 65% of the lidocaine is bound to plasma proteins. Amide local anesthetics are mainly bound to alpha-1-acid glycoprotein and also to albumin. Lidocaine crosses the blood-brain and placental barriers, presumably by passive diffusion.
Metabolism: The main elimination pathway of lidocaine is by liver metabolism. The primary route of lidocaine is N-dealkylation to monoethylglycine xylidine (MEGX), followed by hydrolysis to 2,6-xylidine and hydroxylation to 4-hydroxy-2,6-xylidine. MEGX can also be further dealkylated to glycine xylidine (GX). The pharmacological/toxicological actions of MEGX and GX are similar to, but less potent than those of lidocaine. GX has a longer half-life (about 10 h) than lidocaine and may accumulate during long-term administration.
Excretion: Lidocaine has an elimination half-life of 1.6 h and an estimated hepatic extraction ratio of 0.65. The clearance of lidocaine is almost entirely due to liver metabolism, and depends both on liver blood flow and the activity of metabolizing enzymes. Approximately 90% of the lidocaine administrated intravenously is excreted in the form of various metabolites, and less than 10% is excreted unchanged in the urine. The primary metabolite in urine is a conjugate of 4-hydroxy-2,6-xylidine, accounting for about 70-80% of the dose excreted in the urine.
The elimination half-life of lidocaine following an intravenous bolus injection is typically 1.5 to 2.0 hours. The elimination half-life in neonates (3.2 h) is approximately twice that of adults. The half-life may be prolonged two-fold or more in patients with liver dysfunction. Renal dysfunction does not affect lidocaine kinetics but may increase the accumulation of metabolites.
Special Populations and Conditions
Acidosis increases the systemic toxicity of lidocaine while the use of CNS depressants may increase the levels of lidocaine required to produce overt CNS effects. Objective adverse manifestations become increasingly apparent with increasing venous plasma levels above 6.0 µg free base per mL.
Pharmacokinetics of Chlorhexidine
Absorption: Chlorhexidine is poorly absorbed percutaneously from the GI tract and poorly absorbed following topical application to the skin. Low concentrations of chlorhexidine gluconate appear to be absorbed systemically following intravaginal administration of chlorhexidine gluconate. Following topical application to intact skin, chlorhexidine gluconate is adsorbed onto the outer layers of the skin resulting in a persistent (residual) antimicrobial effect on the skin. Studies using radiolabeled chlorhexidine gluconate indicate that most of the drug remains on the skin, with minimal systemic absorption.
There have been some reports of systemic absorption when chlorhexidine gluconate topical preparations were used as skin cleansers in neonates or infants. Low blood concentrations of chlorhexidine gluconate were detected in 15 of 24 infants who were bathed with chlorhexidine gluconate 4% skin cleanser. Although it has been suggested that chlorhexidine gluconate on the skin may have contaminated heel prick blood samples, 5 of these neonates had venous blood samples drawn that showed low concentrations of the drug. There also was evidence of systemic absorption of low concentrations of chlorhexidine gluconate when a 1% solution of chlorhexidine in alcohol was used in umbilical cord care in preterm neonates; absorption did not appear to occur when the same solution was used in umbilical cord care of full-term neonates or when a dusting powder of chlorhexidine 1% with zinc oxide 3% was used for such care in preterm neonates.
In a study in pregnant women who received a 2% solution of chlorhexidine gluconate intravaginally as a vaginal wash during labour, chlorhexidine concentrations ranging from 0.01–0.083 mcg/mL were detected in the blood (limits of detection 0.01 mcg/mL) of approximately 33% of these women.
Distribution: It is not known whether chlorhexidine gluconate crosses the placenta or is distributed into milk.
Elimination: Any chlorhexidine gluconate absorbed percutaneously following topical application to the skin appears to be mainly excreted unchanged in faeces.
STORAGE AND STABILITY
Store: 15 ˚C to 25 ˚C. Keep out of reach and sight of children.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each mL of Instillagel contains 2% of lidocaine hydrochloride as lidocaine hydrochloride monohydrate and 0.05% chlorhexidine gluconate. It also contains the following non-medicinal ingredients: 0.06% methylparaben, 0.025% propylparaben, hydroxyethylcellulose, sodium hydroxide, propylene glycol and purified water.
Instillagel is available as a sterile, pre-filled syringe made of polypropylene with a butyl rubber stopper piston, and containing 6 or 11 mL of gel. The syringes are packed in boxes of 10 x 6 mL/11 mL. The syringe tip does not support needle attachment.
Any gel not used in a single application should be discarded.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance: Lidocaine Hydrochloride
Proper Name: Lidocaine hydrochloride monohydrate EP
Chemical Name: Lidocaine hydrochloride monohydrate; 2-Diethylamino-N-(2,6-dimethylphenyl) acetamide, monohydrate
Structural Formula:
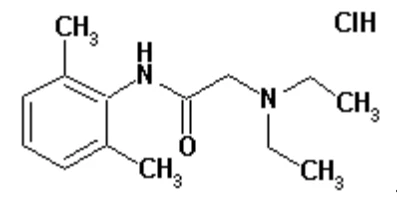 ·H2O
Molecular Formula: C14H22N2O·HCl·H2O
Molecular Weight: 288.8 g/mol
Description: White powder, soluble in water
Physicochemical properties:. pH 4.0-5.5
Drug Substance: Chlorhexidine Gluconate
Proper Name: Chlorhexidine digluconate solution EP/BP
Chemical Name: D-Gluconic acid, compd. with N,N'-bis(4-chlorophenyl)-3,12-diimino-2,4,11,13-tetraazatetradeca- nediimidamide (2:1); 1,1'-Hexamethylenebis(5-(p-chlorophenyl)biguanide) di-D-gluconate
Structural Formula:
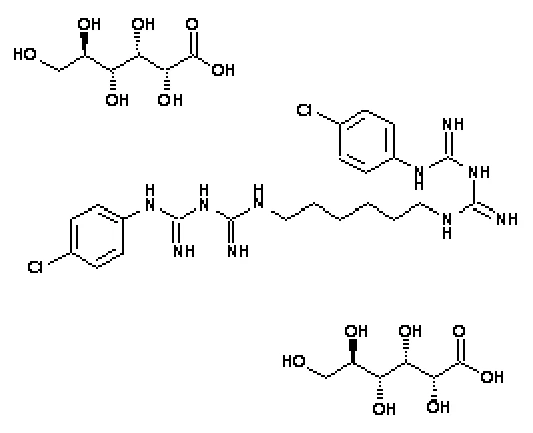
Molecular Formula: C34H54Cl2N10O14
Molecular Weight: 897.77 g/mol
Description: Almost colourless or pale-yellow odourless solution
Physicochemical properties:. pH 5.0-7.0; miscible in water; density 1.06 g/mL