


Product Monograph - Clindamycin Injection SDZ
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intramuscular, intravenous | Solution; clindamycin phosphate equivalent to 150 mg/mL of clindamycin base | Benzyl alcohol 0.9% as preservative, disodium edetate, sodium hydroxide to adjust pH and water for injection. |
INDICATIONS AND CLINICAL USE
Clindamycin Injection SDZ (clindamycin phosphate) is indicated for the treatment of serious infections due to susceptible anaerobic bacteria, such as Bacteroides species, Peptostreptococcus, anaerobic streptococci, Clostridium species and microaerophilic streptococci.
Clindamycin Injection SDZ is also indicated for the treatment of serious infections due to susceptible strains of gram positive aerobic bacteria (staphylococci, including penicillinase-producing staphylococci, streptococci and pneumococci) as well as in the treatment of Chlamydia trachomatis, when the patient is intolerant of, or the organism is resistant to other appropriate antibiotics.
Because of the risk of Clostridium difficile-associated disease (CDAD) as described in the WARNINGS section, before selecting clindamycin the physician should consider the nature of the infection and the suitability of alternative therapy.
Clindamycin Injection SDZ is indicated for the treatment of the following serious infections when caused by susceptible strains of the designated organisms in the conditions listed below:
Lower respiratory infections including pneumonia, empyema, and lung abscess when caused by anaerobes, Streptococcus pneumoniae, other streptococci (except Enterococcus faecalis) and Staphylococcus aureus.
Skin and skin structure infections including cellulitis, abscesses, and wound infections when caused by Streptococcus pyogenes, Staphylococcus aureus and anaerobes.
Gynecological infections including endometritis, pelvic cellulitis, vaginal cuff infections, non-gonococcal tubo-ovarian abscess, salpingitis, and pelvic inflammatory disease when caused by susceptible anaerobes or Chlamydia trachomatis. Clindamycin should be given in conjunction with an antibiotic of appropriate gram negative aerobic spectrum.
Intra-abdominal infections including peritonitis and abdominal abscess when caused by susceptible anaerobes. Clindamycin should be given in conjunction with an antibiotic of appropriate gram negative aerobic spectrum.
Septicemia caused by Staphylococcus aureus, streptococci (except Enterococcus faecalis) and susceptible anaerobes, where the bactericidal efficacy of clindamycin against the infecting organism has been determined in vitro at achievable serum levels.
Bone and joint infections including osteomyelitis and septic arthritis when caused by sensitive strains of Staphylococcus aureus and anaerobes.
Pneumocystis jiroveci pneumonia in patients with AIDS. Clindamycin in combination with primaquine may be used in patients who are intolerant to, or fail to respond to conventional therapy.
Note: Clindamycin Injection SDZ is not indicated in the treatment of meningitis since it penetrates poorly into cerebrospinal fluid, even in the presence of inflamed meninges.
Bacteriologic studies should be performed to determine the causative organisms and their susceptibility to clindamycin.
Indicated surgical procedures and drainage should be performed in conjunction with antibiotic therapy.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Clindamycin Injection SDZ and other antibacterial drugs, Clindamycin Injection SDZ should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Geriatrics (> 65 years of age):
Clinical studies of clindamycin did not include sufficient numbers of patients age 65 and over to determine whether they respond differently from younger patients.
Pediatrics (birth up to 18 years of age):
It is not known if use of clindamycin in the pediatric population is associated with differences in safety or effectiveness compared with adult patients.
CONTRAINDICATIONS
Clindamycin Injection SDZ (clindamycin phosphate) is contraindicated in patients with a known hypersensitivity to preparations containing clindamycin or lincomycin or to any ingredient in the formulation or component of the formulation.
WARNINGS AND PRECAUTIONS
General
In patients with G-6-PD deficiency, the combination of clindamycin with primaquine may cause hemolytic reactions. Reference should also be made to the primaquine product monograph for other possible risk groups for other hematologic reactions (see ADVERSE REACTIONS).
If patients should develop serious hematologic adverse effects, reducing the dosage regimen of primaquine and/or Clindamycin Injection SDZ should be considered (see DOSAGE and ADMINISTRATION).
Clindamycin Injection SDZ (clindamycin phosphate) should be prescribed with caution in atopic individuals.
Clindamycin Injection SDZ must be diluted for intravenous administration. It should not be injected undiluted as an intravenous bolus (see DOSAGE AND ADMINISTRATION).
The use of antibiotics occasionally results in overgrowth of nonsusceptible organisms, particularly yeasts. Should superinfections occur, appropriate measures should be taken as dictated by the clinical situation.
Care should be exercised when treating patients with multiple medications (see DRUG INTERACTIONS).
Gastrointestinal
Clindamycin Injection SDZ should be prescribed with caution in patients with a history of gastrointestinal disease, particularly colitis, inflammatory bowel disease (including regional enteritis and ulcerative colitis), or a history of antibiotic-associated colitis (including pseudomembranous colitis).
NOTE: If diarrhea occurs during treatment, this antibiotic should be discontinued.
Clostridium difficile-associated disease (CDAD)
Clostridium difficile-associated disease (CDAD) has been reported with use of many antibacterial agents, including clindamycin phosphate. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see ADVERSE REACTIONS).
Hepatic/Biliary/Pancreatic
In patients with moderate to severe liver disease, prolongation of the half-life of clindamycin has been found. However, it was postulated from studies that when given every eight hours, accumulation of clindamycin should rarely occur. Therefore, dosage reduction in liver disease is not generally considered necessary. Periodic liver enzyme determinations should be made when treating patients with severe liver disease (see PHARMACOLOGY).
Immune
Serious hypersensitivity reactions including anaphylactoid reactions, severe skin reactions such as drug reaction with eosinophilia and systemic symptoms (DRESS), and dermatological reactions including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN) and acute generalized exanthematous pustulosis (AGEP) have been reported in patients on clindamycin therapy. If a hypersensitivity reaction occurs clindamycin should be discontinued and appropriate therapy should be initiated (see CONTRAINDICATIONS, ADVERSE REACTIONS).
Renal
Clindamycin Injection SDZ dose modification may not be necessary in patients with renal disease. The serum half-life of clindamycin is increased slightly in patients with markedly reduced renal function.
Susceptibility/Resistance
Prescribing Clindamycin Injection SDZ in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Special Populations
Pregnant Women: There are no adequate and well-controlled studies in pregnant women. Safety for use in pregnancy has not been established.
Clindamycin should not be used in pregnancy unless clearly needed and unless the expected benefits to the mother outweigh any potential risks to the fetus. Clindamycin crosses the placenta in humans. After multiple doses, amniotic fluid concentrations were approximately 30% of maternal blood concentrations. Clindamycin was widely distributed in fetal tissues with the highest concentration found in liver.
Clindamycin phosphate injectable formulation contains benzyl alcohol. The preservative benzyl alcohol can cross the placenta (see WARNINGS AND PRECAUTIONS).
Reproduction studies have been performed in rats and mice using subcutaneous and oral doses of clindamycin ranging from 20 to 600 mg/kg/day and have revealed no evidence of impaired fertility or harm to the foetus due to clindamycin except at doses that caused maternal toxicity. In one mouse strain, cleft palates were observed in treated foetuses; this response was not produced in other mouse strains or in other species, and therefore may be a strain specific effect. Oral and subcutaneous reproductive toxicity studies in rats and rabbits revealed no evidence of impaired fertility or harm to the fetus due to clindamycin, except at doses that caused maternal toxicity. Animal reproduction studies are not always predictive of human response.
Nursing Women: Clindamycin has been reported to appear in human breast milk in the range of 0.7 to 3.8 mcg/mL at doses of 150 mg orally to 600 mg intravenously. Because of the potential for serious adverse reactions in nursing infants, clindamycin should not be administered to nursing mothers.
Pediatrics:
Benzyl Alcohol Toxicity
Clindamycin Injection SDZ contains benzyl alcohol. The preservative benzyl alcohol has been associated with serious adverse events, including the "gasping syndrome" and death in pediatric patients. The “gasping syndrome” (characterized by central nervous system depression, metabolic acidosis and gasping respirations) has been reported in preterm and low birth weight newborns. Additional symptoms may include gradual neurological deterioration, seizures, intracranial hemorrhage, hematologic abnormalities, skin breakdown, hepatic and renal failure, hypotension, bradycardia and cardiovascular collapse.
Although normal therapeutic doses of this product ordinarily deliver amounts of benzyl alcohol that are substantially lower than those reported in association with the “gasping syndrome”, the minimum amount of benzyl alcohol at which toxicity may occur is not known. The risk of benzyl alcohol toxicity depends on the quantity administered and the hepatic and renal capacity to detoxify the chemical. Premature and low-birth weight infants may be more likely to develop toxicity.
Practitioners administering this and other medications containing benzyl alcohol should consider the combined daily metabolic load of benzyl alcohol from all sources. When Clindamycin Injection SDZ is administered to the pediatric population (birth to 16 years) appropriate monitoring of organ system functions is desirable.
Geriatrics (> 60 years of age):
Experience has demonstrated that antibiotic-associated colitis may occur more frequently and with increased severity among elderly (> 60 years) and debilitated patients. These patients should be carefully monitored for the development of diarrhea.
Monitoring and Laboratory Tests
Periodic liver and kidney function tests and blood counts should be performed during prolonged therapy when treating patients with severe liver disease.
Routine blood examinations should be done during therapy with primaquine to monitor potential hematologic toxicities.
Serum assays for active clindamycin require an inhibitor to prevent in vitro hydrolysis of clindamycin phosphate.
ADVERSE REACTIONS
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse drug reaction frequencies for the three clindamycin formulations (clindamycin capsules, clindamycin granules for oral solution and clindamycin injection) are based on the clinical data sources from the original drug submission and on the total number of patients enrolled in the clinical trials (N=1787).
Adverse drug reactions that were considered causally related to clindamycin and observed in ≥ 1% of patients are presented below in Table 1. They are listed according to MedDRA system organ class.
Table 1. Adverse Drug Reactions Occurring in ≥ 1% of Patients treated with clindamycin within the Original Clinical Trials
Adverse Reaction System Organ Class / Preferred Term | clindamycin Total N=17871 n (%) |
|---|---|
Gastrointestinal disorders Diarrhea | 26 (1.45) |
Investigations Liver function test abnormal | 66 (3.7) |
Skin and subcutaneous tissue disorders Rash maculopapular | 21 (1.18) |
1clindamycin hydrochloride capsules N=851; clindamycin granules for oral solution N=340; clindamycin phosphate injection N=596
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Less common adverse drug reactions that were considered causally related to clindamycin and observed in < 1% of patients are listed below.
Blood and lymphatic system disorders: Eosinophilia
Gastrointestinal disorders: Nausea, abdominal pain and vomiting.
General disorders and administration site conditions: Local irritation, pain, abscess formation have been seen with IM injection.
Nervous system disorders: Dysgeusia
Skin and subcutaneous tissue disorders: Urticaria, erythema multiforme and pruritus.
Post-market Adverse Drug Reactions
Additional adverse events which have been reported in temporal association with clindamycin phosphate formulations (clindamycin capsules, clindamycin granules for oral solution and clindamycin injection) since market introduction are listed below. Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be established.
Blood and lymphatic system disorders: Agranulocytosis, leucopenia, neutropenia and thrombocytopenia. In clindamycin/primaquine combination studies, serious hematologic toxicities (grade III, grade IV neutropenia or anemia, platelet counts < 50 x 109/L, or methemoglobin levels of 15% or greater) have been observed.
Cardiac disorders: Cardio-respiratory arrest and hypotension have been seen with rapid intravenous administration (see DOSAGE and ADMINISTRATION).
Gastrointestinal disorders: Colitis and pseudomembranous colitis. Clostridium difficile-associated disease (CDAD) has been observed and may manifest as a range of symptoms varying from watery diarrhea to fatal colitis, the onset of which may occur during or after antibacterial treatment (see WARNINGS AND PRECAUTIONS). Esophagitis and esophageal ulcer have been reported with the oral formulations.
General disorders and administration site conditions: Injection site irritation, thrombophlebitis. These reactions can be minimized by deep IM injection and avoidance of indwelling intravenous catheters.
Hepatobiliary disorders: Jaundice
Immune system disorders: Generalized mild to moderate morbilliform-like skin rashes, anaphylactic shock, anaphylactoid reactions, anaphylactic reactions, hypersensitivity, and drug reaction with eosinophilia and systemic symptoms (DRESS).
Infections and infestations: Clostridium difficile colitis
Musculoskeletal: Polyarthritis
Renal and urinary disorders: Renal dysfunction as evidenced by azotemia, oliguria and/or proteinuria
Skin and subcutaneous tissue disorders: Toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), erythema multiforme, dermatitis exfoliative, dermatitis bullous, dermatitis vesiculobullous, rash morbilliform, vaginal infection, vaginitis, acute generalized exanthematous pustulosis (AGEP), angioedema.
Vascular disorders: Thrombophlebitis has been seen with rapid intravenous administration (see DOSAGE AND ADMINISTRATION).
DRUG INTERACTIONS
Overview
Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite, N-desmethylclindamycin. Therefore inhibitors of CYP3A4 and CYP3A5 may reduce clindamycin clearance and inducers of these isoenzymes may increase clindamycin clearance. In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness.
In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1, or CYP2D6 and only moderately inhibits CYP3A4. Therefore, clinically important interactions between clindamycin and coadministered drugs metabolized by these CYP enzymes are unlikely.
Clindamycin has been shown to have neuromuscular blocking properties and potential antagonism with erythromycin and aminoglycosides (see Table 2).
In a clindamycin/primaquine combination study, serious hematologic toxicity has been observed, but the contribution of clindamycin, if any, is unknown (see ADVERSE REACTIONS).
For other physicochemical interactions, please see to compatibility / incompatibility information in section DOSAGE AND ADMINISTRATION.
Drug-Drug Interactions
The drugs listed in the table below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction.
Table 2. Established or Potential Drug-Drug Interactions
| Proper name | Ref | Effect | Clinical comment |
Neuromuscular blocking agents Examples include: atracurium, doxacurium, pancuronium, vecuronium | CS | Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. | Use with caution in patients receiving these agents concurrently. |
| Aminoglycosides | T | Clindamycin is reported to antagonize bactericidal activity of aminoglycosides in vitro. In vivo antagonism has not been demonstrated. | |
| Erythromycin | T | Antagonism has been demonstrated between clindamycin and erythromycin in vitro. Clindamycin and erythromycin may compete for the same protein binding site in bacteria. | Due to possible clinical significance the two drugs should not be administered concurrently. |
| Inhibitors of CYP3A4, CYP3A5 | T | Clearance of clindamycin may be reduced. | |
| Inducers of CYP3A4, CYP3A5 | T | Clearance of clindamycin may be increased. | Monitor for loss of effectiveness. |
| Strong inducers of CYP3A4 such as rifampin | CS and CT | Rifampin appears to dramatically decrease the serum clindamycin concentration. | Serum clindamycin levels and effectiveness should be carefully monitored. A clinically relevant effect of clindamycin on rifampin concentrations is not expected. |
Legend: CS = Case Study; CT = Clinical Trial; T = Theoretical
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Efficacy of clindamycin should be closely monitored in patients using concomitant St. John’s Wort, a CYP3A4 inducer.
Drug-Laboratory Interactions
Interactions between clindamycin and laboratory tests have not been studied.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Clindamycin Injection SDZ dose modification may not be necessary in patients with renal disease. Clindamycin Injection SDZ dosage reduction in liver disease is not generally considered necessary.
Dosage adjustments are not necessary in the elderly with normal hepatic function and normal (age-adjusted) renal function.
Dosage and route of administration should be determined by the severity of the infection, the condition of the patient and the susceptibility of the causative microorganisms.
In cases of β-hemolytic streptococcal infections, treatment should be continued for at least 10 days.
Recommended Dose and Dosage Adjustment
Adults
The usual daily adult dosage of Clindamycin Injection SDZ (clindamycin phosphate) for infections of the intra-abdominal area, female pelvis, and other complicated or serious infections is 2400-2700 mg given in 2, 3 or 4 equal doses. Less complicated infections may respond to lower doses such as 1200-1800 mg/day administered in 3 or 4 equal doses.
Doses of up to 4800 mg daily have been used without adverse effects. Single intramuscular doses of greater than 600 mg are not recommended.
Pelvic Inflammatory Disease
Clindamycin Injection SDZ 900 mg (IV) every 8 hours plus an antibiotic with appropriate gram negative aerobic spectrum administered IV. Treatment with intravenous drugs should continue for at least 48 hours after the patient demonstrates significant clinical improvement. Then continue with appropriate oral therapy to complete 10-14 days total therapy.
Pneumocystis jiroveci pneumonia in patients with AIDS
Clindamycin Injection SDZ 600-900 mg (IV) every 6 hours or 900 mg (IV) every 8 hours in combination with oral daily dose of 15-30 mg of primaquine. Alternatively, clindamycin hydrochloride 300-450 mg may be given orally every 6 hours in combination with 15-30 mg of primaquine for 21 days. If patients should develop serious hematologic adverse effects, reducing the dosage regimen of primaquine and/or Clindamycin Injection SDZ should be considered.
Children over one month of age (IM or IV Administration):
20-40 mg/kg/day in 3 or 4 equal doses. The higher doses would be used for more severe infections.
Neonates under one month of age (IM or IV Administration):
10-20 mg/kg/day in 3 or 4 equal doses. The lower dosage may be adequate for small prematures.
Table 3. IM or IV Administration in Neonates
| Weight | Age | Dose | Route |
|---|---|---|---|
| < 2 kg | 0 - 7 days | 5 mg/kg q12h | IV |
| < 2 kg | 8 - 30 days | 5 mg/kg q8h | IV |
| ≥ 2 kg | 0 - 7 days | 5 mg/kg q8h | IV |
| ≥ 2 kg | 8 - 30 days | 5 mg/kg q6h | IV |
NOTE: Clindamycin Injection SDZ should be administered with caution to newborn infants less than 30 days of age. This product contains benzyl alcohol which has been associated with the fatal “gasping syndrome” in newborn infants. Preterm and low-birth weight infants may be more likely to develop toxicity (see WARNINGS AND PRECAUTIONS).
Administration
Injection site irritation can be minimized by deep IM injection and avoidance of indwelling intravenous catheters.
Parenteral drug products should be inspected visually for particulate matter and discolouration prior to administration, whenever solution and container permit.
IM Administration
Clindamycin Injection SDZ should be used undiluted.
IV Administration
Clindamycin Injection SDZ should be diluted.
Dilution for IV use and Infusion Rates
Clindamycin Injection SDZ must be diluted prior to intravenous administration (see Compatibility with other products for a listing of infusion solutions). The concentration in diluent for infusion should not exceed 18 mg/mL. Infusion rates should NOT EXCEED 30 MG PER MINUTE as indicated below:
Table 4. Dilution and infusion rates
| Dose (mg) | Diluent (mL) | Time (Minutes) |
| 300 | 50 | 10 |
| 600 | 50 | 20 |
| 900 | 100 | 30 |
| 1200 | 100 | 45 |
Administration of more than 1200 mg in a single 1-hour infusion is not recommended.
Alternatively, the drug may be administered in the form of a single rapid infusion of the first dose followed by continuous IV infusion as follows:
Table 5. Infusion rates per clindamycin levels
| To maintain serum clindamycin levels | Rapid infusion rate | Maintenance infusion rate |
| Above 4 mcg/mL | 10 mg/min. for 30 min. | 0.75 mg/min. |
| Above 5 mcg/mL | 15 mg/min. for 30 min. | 1.00 mg/min. |
| Above 6 mcg/mL | 20 mg/min. for 30 min. | 1.25 mg/min. |
Compatibility with other products
Clindamycin Injection SDZ was found to be compatible over a period of 24 hours when 4 mL (600 mg) of Clindamycin Injection SDZ was diluted with 1000 mL of the following commonly used infusion solutions:
Sodium chloride 0.9%
Dextrose 5% in water
Clindamycin phosphate was not stable when added to Dextrose 5% in water plus vitamins. Although Clindamycin Injection SDZ is compatible with Dextrose 5% in water, it is not recommended that Clindamycin Injection SDZ be mixed with any infusion solutions containing B vitamins.
Clindamycin has been shown to be compatible with gentamicin sulfate, tobramycin sulfate and amikacin sulfate. However, a precipitate has been observed when clindamycin and gentamicin are drawn undiluted into the same syringe before subsequent dilution. This precipitate appears to be a zinc-clindamycin complex which results from the zinc content of some gentamicin products. The particle size of the insoluble material is very small and disappears when the admixture is shaken. To avoid this problem, do not mix clindamycin and gentamicin sulfate prior to dilution. Rather, dilute one drug or the other, agitate the solution and then add the second antibiotic.
Incompatibility with other products
When combined with clindamycin in an infusion solution, ampicillin, phenytoin sodium, barbiturates, aminophyllin, calcium gluconate, magnesium sulfate, ceftriaxone sodium, and ciprofloxacin are each physically incompatible with clindamycin phosphate.
Missed Dose:
If a dose is missed, it should be taken as soon as remembered unless it is almost time for the next dose. The dose should not be doubled to make up for a missed dose.
OVERDOSAGE
Reported cases of overdosage with clindamycin phosphate have occurred very infrequently. The majority of these reports have involved infants and young children ranging in age from one day to three years. In this age group, doses as high as 2.4 grams have been used intravenously in 36 hours without observation of adverse reactions. Cardio-respiratory arrest and hypotension have been seen with rapid intravenous administration. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum. No specific antidote is known. The serum elimination half-life of clindamycin is about 3 hours in adults and 2.5 hours in pediatric patients.
| For management of suspected overdosage, contact your regional Poison Control Centre immediately. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Following parenteral administration, biologically inactive clindamycin phosphate is rapidly hydrolyzed in plasma to active clindamycin. Clindamycin exerts its antibacterial effect by binding to the 50 S ribosomal subunit of susceptible bacteria, causing a reduction in the rate of synthesis of nucleic acid, and cessation of protein synthesis.
Clindamycin is primarily bacteriostatic, but may be bactericidal at high concentrations. The mechanism of action of clindamycin in combination with primaquine on Pneumocystis jiroveci is not known (see DETAILED PHARMACOLOGY).
Pharmacodynamics
(see MICROBIOLOGY)
Pharmacokinetics
Absorption: An equilibrium state is reached by the third dose. After intramuscular injection, peak serum levels of clindamycin are reached within 3 hours in adults and 1 hour in pediatric patients. Peak serum levels of clindamycin are achieved immediately after the end of a short-term (10 to 45 minutes) intravenous infusion.
Distribution: Clindamycin binds primarily to alpha-1-acid glycoprotein. Protein binding is concentration dependent, ranging from 60% to 94% at therapeutic serum concentrations.
Clindamycin is distributed into body fluids and tissues including bone, synovial fluid, bile and pleural fluid. Significant levels of clindamycin are not reached in cerebrospinal fluid even in the presence of inflamed meninges. Clindamycin does not cross the blood-brain barrier even in the presence of inflamed meninges. Clindamycin readily crosses the placenta and is distributed into breast milk.
Table 6 records tissue and body fluid levels of clindamycin base following administration of clindamycin phosphate in adult patients undergoing surgical procedures.
Table 6: Clindamycin concentrations in Tissues and Fluids
| Specimen | Dosage of Clindamycin phosphate | Tissue or Fluid Level |
|---|---|---|
| Bone | IM 300 mg every 8 hours | 6.4 mcg/g |
| Bone | IM 600 mg every 8 hours | 1.44 mcg/g |
| Bone | IV 600 mg every 8 hours | 0.75 mcg/g |
| Bone Marrow | IM 600 mg every 8 hours | 10.83 mcg/g |
| Bile | IV 300 mg every 6 hours | 2.70 mcg/g |
| Synovial Fluid | IM 300 mg every 8 hours | 4.87 mcg/mL |
| Synovial Fluid | IM 150 mg every 12 hours | 15.6 mcg/mL |
| Specimen | Dosage of Clindamycin phosphate | Tissue or Fluid Level |
|---|---|---|
| Pleural Fluid | IV 450 mg every 8 hours | 3.65 mcg/mL |
Table 7: Average Peak Serum Concentrations After Dosing with Clindamycin Phosphate
| Clindamycin Phosphate Dosage Regimen | Clindamycin mcg/mL | Clindamycin Phosphate mcg/mL |
|---|---|---|
| Healthy Adult Male (Post Equilibrium) | ||
| 300 mg IV in 10 min., q8h | 7 | 15 |
| 600 mg IV in 20 min., q8h | 10 | 23 |
| 900 mg IV in 30 min., q12h | 11 | 29 |
| 1200 mg IV in 45 min., q12h | 14 | 49 |
| 300 mg IM q8h | 6 | 3 |
| 600 mg IM q12h* | 9 | 3 |
| Children (first dose)* | ||
| 5-7 mg/kg IV in 1 hour | 10 | |
| 3-5 mg/kg IM | 4 | |
| 5-7 mg/kg IM | 8 |
* Data in this group from patients being treated for infection.
Metabolism: In vitro studies in human liver and intestinal microsomes indicate clindamycin is predominantly oxidized by CYP3A4, with minor contribution from CYP3A5, to form clindamycin sulfoxide and a minor metabolite, N-desmethylclindamycin.
Excretion: Approximately 10% of the microbiologically active form is excreted in the urine and about 4% in the feces. The remainder is excreted as biologically inactive metabolites.
Clindamycin phosphate disappears rapidly from the serum; the average elimination half-life is 6 minutes following IM or IV administration in adults. The serum elimination half-life of clindamycin is about 3 hours in adults and 2.5 hours in pediatric patients.
Special Populations and Conditions
Geriatrics: Pharmacokinetic studies with clindamycin have shown no clinically important differences between young and elderly subjects with normal hepatic function and normal (age-adjusted) renal function after oral or intravenous administration. Therefore, dosage adjustments are not necessary in the elderly with normal hepatic function and normal (age-adjusted) renal function.
Hepatic Impairment: Six patients with impaired liver function had a mean serum elimination half-life of 4.5 hours (range 4.2 to 7.0 hours) (see DETAILED PHARMACOLOGY).
Renal Impairment: Four patients with impaired renal function had a mean serum elimination half-life of 3.0 hours (range 1.7 to 5.6 hours) (see DETAILED PHARMACOLOGY).
SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
STORAGE AND STABILITY
Store Clindamycin Injection SDZ at controlled room temperature, (15 to 25 °C). When diluted as recommended, Clindamycin Injection SDZ is compatible for 24 hours.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each mL of undiluted Clindamycin Injection SDZ contains clindamycin phosphate equivalent to 150 mg of clindamycin base, benzyl alcohol 9 mg as preservative, disodium edetate 0.5 mg, sodium hydroxide to adjust pH and water for injection.
Clindamycin Injection SDZ is available in 2 mL and 4 mL ampoules, in boxes of 10 and in 6 mL vials, boxes of 10.
Discard unused portion.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Clindamycin phosphate
Chemical Name: 1) L-threo-α-D-galacto-Octopyranoside, methyl 7-chloro-6,7,8-trideoxy-6-[[(1-methyl-4-propyl-2-pyrrolidinyl) carbonyl] amino]-1-thio, 2-(dihydrogen phosphate), (2S-trans);
- 2) Methyl 7-chloro-6,7,8-trideoxy-6-(1-methyl-trans-4-propyl-L-2- pryrrolidinecarboxamido)-1-thio-L-threo-α-D-galacto- octopyranoside 2-(dihydrogen phosphate);
- 3) 7-(S)-Chloro-7-deoxylincomycin 2-phosphate.
Molecular Formula: C18H34ClN2O8PS
Molecular Weight: 505 g/mol
Structural Formula:
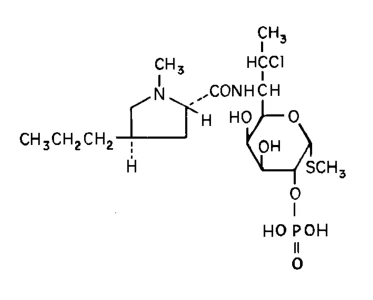
Description:
Clindamycin phosphate is a water soluble ester of clindamycin and phosphoric acid. It is a white to off-white crystalline hygroscopic powder that is odourless or nearly odourless. It has a pH of 3.5 to 4.5 and melts with decomposition at about 175°C. The partition coefficient is 0.03.
CLINICAL TRIALS
The authorized indications were based on safety and efficacy clinical trials which were conducted with clindamycin phosphate.
DETAILED PHARMACOLOGY
Absorption and Excretion in Normal Human Volunteers
Clindamycin phosphate is essentially inactive as the phosphate ester. Chemical or enzymatic hydrolysis of clindamycin phosphate is necessary to obtain the antibiotic activity of the clindamycin base. When tested with commercial human serum, clindamycin at a concentration of 1 mcg/mL of clindamycin free base is 92.8% protein bound.
Intramuscular: Serum levels and urinary excretion of clindamycin and clindamycin phosphate were measured after the single administration of 300 mg (2 mL) base equivalent of clindamycin phosphate and multiple dose administration (300 mg every 8 hours for 14 days). The results are shown in Table 8.
Table 8: Mean serum levels in mcg/mL of free clindamycin and clindamycin phosphate after 1st and 43rd IM dose of 300 mg (2 mL) of clindamycin phosphate
| Hours after Injection | |||||||||||||||
| 1st Injection | 43rd Injection | ||||||||||||||
| 0.5 | 1 | 1.5 | 2 | 3 | 4 | 7.5 | 0 | 7.5 | |||||||
Free clindamycin | 2.05 | 3.16 | 3.66 | 3.88 | 3.89 | 3.56 | 1.94 | 2.85 | 2.67 | ||||||
Clindamycin phosphate | 2.40 | 1.99 | 1.75 | 1.33 | 0.86 | 0.59 | 0.03 | 0.04 | 0.06 | ||||||
The apparent half-life of clindamycin phosphate is 3.5 to 4.5 hours. Bioavailability of clindamycin from its phosphate was estimated to be greater than 75%, based on urinary excretion of free clindamycin bioactivity (0 to 12 hours). During the multiple dose studies (300 mg every 8 hours for 14 days), there was no evidence of drug accumulation or enzyme induction.
Intravenous: Determination of serum levels of clindamycin and clindamycin phosphate after intravenous infusion of 300 to 1200 mg free base equivalents of clindamycin phosphate indicated that the concentrations of free clindamycin and intact phosphate were approximately equivalent during rapid infusion (see Table 9). The mean half-life of free clindamycin given by intravenous infusion is 2.28 hours for a 300 mg dose, 2.94 hours for a 600 mg dose, 3.27 hours for a 900 mg dose and 3.07 hours for a 1200 mg dose.
During maintenance infusion, free clindamycin (3.6 to 6.9 mcg/mL) was the predominant species in circulation. Over the total infusion period (0 to 8 hours) clindamycin and clindamycin phosphate were excreted in the urine in amounts up to 12.3% and 5.1%, respectively, of the administered clindamycin phosphate dose. There was no indication that the capacity to excrete clindamycin in the urine had been taxed by these dosages.
Table 9: Mean serum levels in mcg/mL of free clindamycin and clindamycin phosphate after intravenous infusion of 300, 600, 900 and 1200 mg of clindamycin phosphate
| Dosage and Rate of | Time after infusion began (in hours) | |||||
| Infusion | A* | B* | 1.5 | 4 | 12 | |
| 300 mg in | Free clindamycin | 5.40 | 4.36 | 3.49 | 1.66 | 0 |
| 10 minutes | Clindamycin Phosphate | 14.66 | 2.35 | 0.43 | 0.13 | - |
| 600 mg in | Free clindamycin | 8.42 | 6.70 | 5.88 | 3.04 | 0.62 |
| 20 minutes | Clindamycin Phosphate | 26.98 | 2.24 | 0.58 | 0.28 | 0.02 |
| 900 mg in | Free clindamycin | 10.37 | 8.02 | 7.10 | 4.18 | 1.08 |
| 30 minutes | Clindamycin Phosphate | 31.20 | 3.18 | 1.29 | 0.25 | 0 |
| 1200 mg in | Free Clindamycin | 13.11 | 15.87 | 10.37 | 5.90 | 1.16 |
| 45 minutes | Clindamycin Phosphate | 43.98 | 49.11 | 4.07 | 0.43 | 0 |
* Time A Time B
300 mg 0.17 hr 0.5 hr
600 mg 0.33 hr 0.75 hr
900 mg 0.5 hr 0.75 hr
1200 mg 0.5 hr 0.75 hr
Absorption and excretion in patients with impaired hepatic or renal function
In a series of six patients with hepatic insufficiency and four patients with renal insufficiency, a single intravenous infusion of 300 mg of clindamycin phosphate was given over a period of 30 minutes. The results of these studies are summarized in Tables 10, 11, 12 and 13.
Table 10: Liver function tests in patients with impaired liver function
Patient Number | Total serum bilirubin | SGOT (K units) | SGPT (K units) | Alkaline Phosphatase | LDH |
| 1 | 7.0 | 150 | - | 150 | 180 |
| 2 | 6.6 | 155 | 74 | 110 | - |
| 3 | 8.0 | 35 | - | 50 | 100 |
| 4 | 1.6 | 135 | - | 235 | - |
| 5 | > 10 | 2200 | - | 130 | 340 |
| 6 | > 10 | 240 | - | 185 | 160 |
Table 11: Serum levels of free clindamycin in mcg/ml in patients with hepatic insufficiency, 300 mg clindamycin phosphate infused over 30 minutes.
Patient Number | Time after start of infusion in hours | Elimination Half-Life | ||||||||||||||
| 0.5 | 1.5 | 3 | 6 | 12 | 24 | (hrs) | ||||||||||
| 1 | 7.19 | 3.61 | 3.36 | 1.96 | 0.74 | - | 4.9 | |||||||||
| 2 | 11.60 | 6.32 | 5.25 | 4.04 | 2.23 | 1.30 | 7.0 | |||||||||
| 3 | 8.68 | 7.16 | 5.15 | 3.68 | 1.25 | 0.88 | 4.4 | |||||||||
| 4 | 17.75 | 8.60 | 6.08 | 2.77 | 0.83 | 0.0 | 4.8 | |||||||||
| 5 | 8.42 | 4.93 | 3.84 | 2.49 | 0.75 | 0.45 | 4.2 | |||||||||
| 6 | 9.51 | 4.63 | 3.38 | 2.66 | 1.31 | 0.0 | 5.8 | |||||||||
Table 12: Renal function tests in patients with impaired renal function
| Patient Number | BUN | Serum Creatinine | Urine Albumin | Urine Sugar |
| 1 | 87 | 3.4 | 2+ | 3+ |
| 2 | 73 | 3.2 | 2+ | trace |
| 3 | 78 | 6.4 | 4+ | 0 |
| 4 | 59 | 1.4 | 0 | 0 |
Table 13: Serum levels of free clindamycin in mcg/mL in patients with impaired renal function after 300 mg clindamycin infused over 30 minutes.
Patient Number | Time after start of infusion in hours | Elimination Half-Life | |||||||||||||||
| 0.5 | 1.5 | 3 | 6 | 12 | 24 | (hrs) | |||||||||||
| 1 | 12.07 | 7.35 | 5.26 | 2.30 | 1.08 | 0.0 | 3.0 | ||||||||||
| 2 | 12.00 | 4.15 | 3.36 | 1.90 | 0.66 | 0.42 | 3.6 | ||||||||||
| 3 | 15.25 | 10.63 | 7.52 | 5.80 | - | 1.41 | 5.6 | ||||||||||
| 4 | 11.26 | 7.29 | 3.39 | 1.60 | 0.0 | 0.0 | 1.7 | ||||||||||
Biologically inactive clindamycin phosphate is converted to active clindamycin. By the end of short-term intravenous infusion, peak serum levels of active clindamycin are reached.
After intramuscular injection of clindamycin phosphate, peak levels of active clindamycin are reached within 3 hours in adults and 1 hour in pediatric patients. Serum level curves may be constructed from IV peak serum levels as given in Table 14 by application of elimination half-lives (see Excretion).
Table 14. Average Peak and Trough Serum Concentrations of Active Clindamycin After Dosing with Clindamycin Phosphate
| Dosage Regimen | Peak mcg/mL | Trough mcg/mL | |||
|---|---|---|---|---|---|
Healthy Adult Males (Post equilibrium) | |||||
| 600 mg IV in 30 min q6h | 10.9 | 2.0 | |||
| 600 mg IV in 30 min q8h | 10.8 | 1.1 | |||
| 900 mg IV in 30 min q8h | 14.1 | 1.7 | |||
| 600 mg IM q12h* | 9 | ||||
| Pediatric Patients (first dose)* | |||||
| 5-7 mg/kg IV in 1 hour | 10 | ||||
| 5-7 mg/kg IM | 8 | ||||
| 3-5 mg/kg IM | 4 | ||||
*Data in this group from patients being treated for infection.
Serum levels of clindamycin can be maintained above the in vitro minimum inhibitory concentrations for most indicated organisms by administration of clindamycin phosphate every 8 to 12 hours in adults and every 6 to 8 hours in pediatric patients, or by continuous intravenous infusion. An equilibrium state is reached by the third dose.
Excretion: The mean elimination half-time for normal healthy men given 300 mg of clindamycin phosphate in a 10 minute infusion was 2.5 hours. The six patients with impaired liver function had a mean elimination half-time of 4.5 hours and those with impaired renal function a mean elimination half-time of 3.0 hours.
MICROBIOLOGY
Clindamycin phosphate is inactive in vitro, but is rapidly converted in vivo to the antibacterially-active clindamycin.
In order to assess the significance of in vitro antibiotic activity against bacterial species, it is necessary to compare the organism's minimum inhibitory concentration (MIC) to the defined susceptibility interpretive breakpoints for the antibiotic. Table 15 identifies the currently-accepted NCCLS (1990) MIC interpretative breakpoints for clindamycin.
Table 15. Susceptibility Interpretive Criteria for Clindamycin
| Pathogen | Susceptibility Interpretive Criteria | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Minimal Inhibitory Concentrations (MIC in mcg/mL) | Disk Diffusion (Zone Diameters in mm) | ||||||||||
| Staphylococcus spp. | S ≤ 0.5 | I 1-2 | R ≥ 4 | S ≥ 21 | I 15-20 | R ≤ 14 | |||||
| Streptococcus pneumoniae and other Streptococcus spp. | ≤ 0.25 | 0.5 | ≥ 1 | ≥ 19 | 16-18 | ≤ 15 | |||||
| Anaerobic Bacteria | ≤ 2 | 4 | ≥ 8 | NA | NA | NA | |||||
NA = not applicable
The reported clindamycin MIC90 value (i.e., the concentration of clindamycin that inhibits 90% of test isolates) was utilized as the most descriptive measure of clindamycin activity. Where the data from more than one study are summarized, the weighted average MIC90 value was calculated to account for differences in the number of strains in each study.
The in vitro susceptibility of clinical isolates to clindamycin is presented in Table 16 (gram-positive aerobic bacteria), Table 17 (gram-negative aerobic bacteria), Table 18 (gram-positive anaerobic bacteria), Table 19 (gram-negative anaerobic bacteria) and Table 20 (Chlamydia spp and Mycoplasma spp).
Table 16: In Vitro activity of clindamycin against gram-positive aerobic bacteria a
| Organism | Nb | MIC90 Range c | MIC90d |
| Bacillus cereus | 46 | 1 | 1 |
| Corynebacterium diphtheriae | 192 | 0.1 | 0.1 |
| Listeria monocytogenes | 218 | 1-8 | 2.22 |
| Staphylococcus aureus (methicillin-susceptible) | 286 | 0.12-2 | 0.50 |
| Staphylococcus saprophyticus | 57 | 0.12 - 0.25 | 0.16 |
| Streptococcus agalactia | 59 | ≤ 0.06 - 0.50 | 0.15 |
| Streptococcus bovis | 22 | 0.04 | 0.04 |
| Streptococcus pneumonia (penicillin-susceptible) | 660 | 0.03-0.25 | 0.23 |
| Streptococcus pyogenes | 141 | 0.13-0.25 | 0.08 |
| Streptococcus spp, Group B | 38 | ≤ 0.12-0.25 | 0.15 |
| Streptococcus spp, Group C | 30 | ≤ 0.12 - 0.50 | 0.22 |
| Streptococcus spp. Group G | 34 | 0.06-0.50 | 0.31 |
| Streptococcus spp, viridans Group (penicillin-susceptible) | 67 | ≤ 0.06-1.6 | 0.53 |
a clinical efficacy has not been established for some of these species
b N, total number of isolates
c Range of reported MIC90 values
d MIC90 for single study or weighted average MIC90 for two or more studies
| Table 17: In Vitro activity of clindamycin against gram-negative aerobic bacteria a | |||
|---|---|---|---|
| Organism | Nb | MIC90 Range c | MIC90 d |
| Campylobacter jejuni | 449 | 0.39-8 | 1.7 |
| Campylobacter fetus | 41 | 1 - 1.6 | 1.2 |
| Campylobacter coli | 31 | 0.50 | 0.50 |
| Gardnerella vaginalis | 156 | ≤ 0.06 - 0.39 | 0.3 |
| Helicobacter pylori | 47 | 2-3.1 | 2.6 |
| Neisseria gonorrhoeae (β-lactamase-negative) | 77 | 4 | 4 |
| Neisseria gonorrhoeae (β-lactamase-positive) | 54 | 2 | 2 |
a clinical efficacy has not been established for some of these species
b N, total number of isolates
c Range of reported MIC90 values
d MIC90 for single study or weighted average MIC90 for two or more studies
Table 18: In Vitro activity of clindamycin against gram-positive anaerobic bacteria a
| Organism | Nb | MIC90 Range c | MIC90 d |
| Actinomyces israelii | 46 | 0.12 | 0.12 |
| Actinomyces spp | 38 | 0.50 - 1 | 0.8 |
| Clostridium botulinum | 224 | 4 | 4 |
| Clostridium difficile | 191 | 4->256 | 57.7 |
| Clostridium novyi | 18 | 2 | 2 |
| Clostridium perfringens | 386 | 0.25-8 | 3.4 |
| Clostridium ramosum | 98 | 4-12.5 | 8.3 |
| Eubacterium spp | 45 | 0.4-2 | 1.1 |
| Lactobacillus spp | 88 | 0.50 - 1 | 0.8 |
| Peptostreptococcus anaerobes | 283 | 0.25 - 0.50 | 0.4 |
| Peptostreptococcus asaccharolyticus | 268 | 0.25 - 2 | 1.5 |
| Peptostreptococcus magnus | 90 | 2 | 2 |
| Peptostreptococcus prevotii | 87 | 0.12 - 4 | 2.9 |
| Peptostreptococcus tetradius | 28 | 0.5 | 0.5 |
| Anaerobic gram-positive cocci | 247 | 0.5 - 1 | 0.9 |
| Propionibacterium acnes | 267 | 0.10 - 0.25 | 0.2 |
| Propionibacterium spp | 71 | 0.12 - 0.20 | 0.16 |
a clinical efficacy has not been established for some of these species.
b N, total number of isolates
c Range of reported MIC90 values
d MIC90 for single study or weighted average MIC90 for two or more studies
Table 19: In Vitro activity of clindamycin against gram-negative anaerobic bacteria a
| Organism | Nb | MIC90 Range c | MIC90 d |
|---|---|---|---|
| Bacteroides fragilis group | 4284 | 0.5-8 | 2.45 |
| Bacteroides fragilis | 2002 | ≤ 0.20 - 4 | 2.22 |
| Bacteroides melaninogenicus | 224 | ≤ 0.03-0.50 | 0.07 |
| Bacteroides spp | 141 | ≤ 0.06 - 0.50 | 0.31 |
| Bacteroides bivius | 155 | ≤ 0.03 - ≤ 0.05 | ≤0.11 |
| Bacteroides disiens | 33 | ≤ 0.03 - ≤ 0.06 | ≤0.05 |
| Fusobacterium spp | 330 | ≤ 0.10 - 2 | 0.85 |
| Mobiluncus mulieris | 10 | 0.06 | 0.06 |
| Mobiluncus curtisii | 12 | 0.12 | 0.12 |
| Veillonella spp | 38 | 0.06 - 0.25 | 0.20 |
a clinical efficacy has not been established for some of these species.
b N, total number of isolates
c Range of reported MIC90 values
d MIC90 for single study or weighted average MIC90 for two or more studies
Clindamycin has demonstrated in vitro activity against Chlamydia trachomatis and Mycoplasma spp (see Table 20). For Chlamydia trachomatis, the MIC90 for clindamycin is reached at 2.3 mcg/mL; in vitro synergism with gentamicin has also been demonstrated.
Table 20: In Vitro activity of clindamycin against Chlamydia spp and Mycoplasma spp a
| Organism | Nb | MIC90 Range c | MIC90 d |
| Chlamydia trachomatis | 84 | 0.5 - 5.9 | 2.3 |
| Mycoplasma hominis | 106 | 0.25 - 0.8 | 0.58 |
| Mycoplasma pneumoniae | 9 | 4 | 4 |
a clinical efficacy has not been established for some of these species
b N, total number of isolates
c Range of reported MIC90 values
d MIC90 for single study or weighted average MIC90 for two or more studies
The in vitro activity of clindamycin in combination with primaquine has not been determined.
Development of resistance to clindamycin by staphylococci is slow and stepwise rather than rapid and streptomycin-like. Clindamycin, like lincomycin, participates in the dissociated cross-resistance phenomenon with erythromycin. Clindamycin is not cross-resistant with penicillin, ampicillin, tetracycline or streptomycin. It is, however, cross-resistant with lincomycin.
Resistance to clindamycin may occur by one of several mechanisms. Resistance does not appear to be caused by reduced drug uptake but rather is generally due to alterations in the bacterial target site (50S ribosomal subunit). Resistance can result from either changes in a ribosomal protein at the receptor site or a change in the 23S ribosomal RNA by methylation of adenine. Rare isolates of staphylococci and some veterinary isolates of streptococci may enzymatically inactivate clindamycin by adenylation. Plasmid-mediated transferable resistance to clindamycin (and erythromycin) in B.fragilis was reported in 1979. Despite the existence of multiple resistance mechanisms, the reported incidence of clindamycin resistance in the B.fragilis group has remained relatively low (averaging 5.3% from 1970-1987 in over 7600 isolates). Susceptibility of isolates to clindamycin should be assessed by individual MIC determinations.
TOXICOLOGY
Acute Toxicity
The results of LD50 studies are shown in Table 21:
Table 21: LD50 Results
| Species | Route | LD50 (mg/kg) |
|---|---|---|
| Adult Mouse | IP | 1145 |
| Adult Mouse | IV | 855 |
| Adult Rat | SC | >2000 |
| Adult Rat | PO | 1832 |
| Newborn Rat | SC | 179 |
Tables 22 and 23 summarize toxicity and teratology studies. Table 24 summarizes human studies.
Teratogenic and Reproductive Studies in the Rat and Rabbit
Oral and subcutaneous reproductive toxicity studies in rats and rabbits revealed no evidence of impaired fertility or harm to the fetus due to clindamycin, except at doses that caused maternal toxicity.
In oral embryo fetal development studies in rats and subcutaneous embryo fetal development studies in rats and rabbits, no developmental toxicity was observed except at doses that produced maternal toxicity.
Mutagenicity
Clindamycin phosphate did not show evidence of mutagenicity when tested in the Ames Assay (Salmonella/Microsome Test) or the Micronucleus Test.
Carcinogenesis
Long term studies in animals have not been performed with clindamycin to evaluate carcinogenic potential.
Table 22. TOXICITY STUDIES
Type of Study | Species | Route | Dose mg/kg/d | Duration | Conclusions |
|---|---|---|---|---|---|
| Tolerance | Rabbit N = 3 | IM | 100, 200, 300 | Single dose | Slight to moderate local irritation |
| Tolerance | Rat N = 10 | SC | 120 | 6 days | Local evidence of multiple epidermal breakdown with scab formation over the injection site was present in most rats. No systemic evidence of drug effect was detected at necropsy. Organ weights were not significantly different from control animals and likewise no significant deviations of hematologic data were noted among treated animals. |
| Tolerance | Dog N = 3 | IM | 60 | 6 days | These doses were well tolerated by the dogs. Serum transaminase values were elevated terminally with SGOT values increasing in advance of SGPT values, suggesting that the source of these changes was the injected muscles. No other evidence of treatment-related changes was noted in terminal hemograms, blood chemistry values and urinalyses. Gross pathological changes were confined to the injection sites where there were signs of slight hemorrhage and edema. |
Subacute Toxicity | Rat N = 10 | SC | 30, 60, 90 | 1 month | No drug-related systemic effects were observed. Local inflammatory changes were seen at all three dose levels with focal necrosis of the subcutaneous tissues and overlying epidermis seen in the 60 and 90 mg/kg groups. |
Subacute Toxicity | Dog N = 9 | IM | 30, 60, 90 | 1 month | Under the conditions of this study, clindamycin phosphate was found to be mildly to moderately irritating. Elevations of SGOT and SGPT were noted in these dogs and were thought to be due to muscle damage caused by the injections. Other blood evaluations and liver function tests were in the normal range. A slight dose-related increase in liver weight was indicated on the basis of per cent of body weight, but no morphologic evidence of drug effect on the liver was obtained. |
Subacute Toxicity | Dog N = 8 | IV | 60, 120 | 1 month | No drug related effects were observed in any of the animals during or after the intravenous administrations. In particular, there was no evidence of drug-induced hemolysis or drug-related changes in the cephalic veins on both gross and microscopic examination. |
Table 23. TERATOLOGY STUDIES
| Species | Route | Dose mg/kg/day | Duration | Conclusions |
|---|---|---|---|---|
| Rat | SC | 0, 100, 180 | Gestation days 6-15 | Not teratogenic |
| Mouse | SC 2 strains | 100, 180 | Gestation days 6-15 | A low incidence of cleft palate occurred in one strain in the initial experiment and as a result, the study was repeated twice with no abnormalities noted. The study in the second strain of mice was completely within normal limits. |
| Rat | PO | 100, 300 | No biologically significant effect on the reproductive parameters studied was noted. Pups from treated females were slightly lighter at birth and weaning but post-natal survival was not affected by this slight weight reduction. None of the pups which were dead at birth, died before weaning, or were sacrificed at weaning, exhibited significant morphologic abnormalities. |
| Table 24 . HUMAN TOLERANCE STUDIES | ||||||||||||||||||||
| N | Route | Dose | Duration | Conclusions | ||||||||||||||||
| 8 | IM | 300 mg clindamycin phosphate | Single dose | Subjectively, one patient had mild pain, four had moderate pain and two had marked pain which did not occur immediately, but reached its maximum at 10 to 30 minutes after injection and subsided to a mild ache 30 to 60 minutes later. Clinical laboratory findings were all normal. | ||||||||||||||||
| 8 | IM | 600 mg clindamycin phosphate | Single dose | Only three patients had short-lived moderate pain 30 minutes after injection. | ||||||||||||||||
| 24 | IM | Group 1 (8 patients): 300 mg clindamycin phosphate | Every 8 hr (total 43 injections) | One volunteer in each of the clindamycin phosphate and Lincocin group was removed from the study after 41 injections due to local intolerance. One volunteer from sodium chloride group left on day 5 (after 15 injections) complaining that the injections were too painful. Three Lincocin volunteers were dropped from the study on day 8 (after 24 injections); one due to local discomfort and a suspected viral illness; one due to a rash and one because of headache and tinnitus. In general, in these small groups, clindamycin phosphate was as well tolerated as Lincocin. There was no necrosis in any case. Pain, tenderness, swelling and induration were typically mild. Two clindamycin phosphate-treated volunteers developed mild cases of loose stools, lasting two to ten days during treatment. Audiometric examinations showed no change from pre-treatment examinations. Clinical laboratory findings did not indicate any drug-induced toxicity. A marked rise in creatinine phosphokinase was seen in both the clindamycin phosphate and Lincocin groups. SGOT also rose above normal in the clindamycin group, but not in the Lincocin group. SGPT findings remained within normal range in all groups. These changes are consistent with changes due to muscle irritation and not attributed to liver damage. | ||||||||||||||||
| Group 2 (8 patients): 2 mL of sodium chloride injection USP | ||||||||||||||||||||
| Group 3 (8 patients): 600 mg Lincocin sterile solution | ||||||||||||||||||||
| 20 | IV | Dosing Schedule | Five days | Tolerance observations included blood pressure, pulse, respiratory rate and lead II electrocardiographic monitoring prior to, every 5 minutes during and at the end of each infusion. A 12 lead electrocardiographic tracing was done prior to treatment and after the 12th infusion. Audiograms were performed prior to treatment, within 48 hours after and 90 days after the 12th infusion. Subjects were watched closely for signs of local intolerance during each infusion period. Prior to the 1st, 5th, 9th and 4 hours after the 12th infusion, blood and urine samples were obtained for the following clinical laboratory determinations: complete blood count (CBC); complete urinalysis; serum glutamic oxalacetic transaminase (SGOT); serum alkaline phosphatase; serum creatinine; total, direct and indirect bilirubin; urine bilirubin; and serum haptoglobin. None of the tolerance data indicated any clinically significant side effects from the intravenous infusion of clindamycin phosphate | ||||||||||||||||
Subject Nos. | Treatment Group | Dose (mg) | Infusion Regimen | Infusion Rate | Total Daily Dose (mg) | |||||||||||||||
| 1-6 | A | 300 | 4 doses BID 4 doses TID 4 doses QID | 30 mg/minute for 10 minutes | 600 900 1200 | |||||||||||||||
| 7-12 | B | 600* | 4 doses BID 4 doses TID 4 doses QID | 30 mg/minute for 20 minutes | 1200 1800 2400 | |||||||||||||||
| 13-16 | C | 900 | 4 doses BID 4 doses TID 4 doses QID | 30 mg/minute for 30 minutes | 1800 2700 3600 | |||||||||||||||
| 17-20 | D | 1200 | 4 doses BID 4 doses TID 4 doses QID | 26.7 mg/minute for 45 minutes | 2400 3600 4800 | |||||||||||||||
- Subjects 7 and 8 received 1200 mg in 20 minutes on infusion #1
REFERENCES
- 1. Bartlett JG, Onderdonk, AB, Cisneros, RL. Clindamycin-Associated Colitis in Hamsters: Protection with Vancomycin. Gastroenterology 1977; 73: 772-76.
- 2. Bartlett JG, Chang T, Onderdonk, AB. Comparison of Five Regimens for Treatment of Experimental Clindamycin-Associated Colitis. J Infect Dis 1978; 138: 81-86.
- 3. Bartlett JG, Chang T, Taylor NS, Onderdonk, AB. Colitis Induced by Clostridium difficile. Rev Infect Dis 1979; 1: 370-78.
- 4. Bartlett JG, Miao PVW, Gorbach SL. Empiric treatment with clindamycin and gentamicin of suspected sepsis due to anaerobic and aerobic bacteria. J Infec Dis 1977; 135 (Suppl): S80-5.
- 5. Black JR, Feinberg J, Murphy RL, Fass RJ, Finkelstein D, Akil B, et al. Clindamycin and primaquine therapy for mild-to-moderate episodes of Pneumocystis carinii pneumonia in patients with AIDS: AIDS Clinical Trials Group 044. Clin Inf Dis 1994;18:905-13.
- 6. Browne RA, Fekety R, Silva J, Boyd DI, Work CO, Abrams GD. The Protective Effect of Vancomycin on Clindamycin-Induced Colitis in Hamsters. Johns Hopkins Medical Journal 1977; 141: 183-92.
- 7. Burdon DW, Brown JD, George RH, Arabi Y, Alexander-Williams J, Keighley MRB. Pseudo-membranous Colitis Caused by Clostridia. (Letter) N Eng J Med 1978; 299:48.
- 8. Burdon DW, Brown JD, Young DJ, Arabi Y, Shinagawa N, Alexander-Williams J, Keighley MR, George RH. Antibiotic Susceptibility of Clostridium difficile. J Antimicrob Chemother 1979; 5: 307-10.
- 9. Carlisle HN, Saslaw S. Therapy of staphylococcal infections in monkeys. VI. Comparison of clindamycin, erythromycin, and methicillin, Applied Microbiology 1971 March; 21: 440-46.
- 10. Fass RJ, Saslaw S. Clindamycin: clinical and laboratory evaluation of parenteral therapy. Am J Med Sci 1972; 263 (5): 369-82.
- 11. Feigin RD, Pickering LK, Anderson D, Keeney RE, Shackleford PG. Clindamycin treatment of osteomyelitis and septic arthritis in children. Pediatrics 1975; 55 (2): 213-23.
- 12. Fekety R. Prevention and Treatment of Antibiotic-Associated Colitis. Microbiology - American Society for Microbiology, Washington, D.C. 1979: 276-79.
- 13. George WL, Kirby BD, Sutter VL, Finegold SM. Antimicrobial Susceptibility of Clostridium difficile. Microbiology - American Society for Microbiology, Washington, D.C. 1979; 267-71
- 14. Gordon RC, Regamey C, Kirby WMM: Serum protein binding of erythromycin, lincomycin, and clindamycin. J Pharm Sci 1973;62(7):1074-1076.
- 15. Gudiol F, Manresa F, Pallares R, Dorca J, Rufi G, Boada J, Ariza X, Casanova A, Viladrich PF. Clindamycin vs penicillin for anaerobic lung infections. Arch Intern Med 1990; 150: 2525-29.
- 16. Gunning JE. A comparison of piperacillin and clindamycin plus gentamicin in women with pelvic infections. Surg Gynecol Obstet 1986; 163 (2): 156-62.
- 17. Humphrey CD, Condon CW, Cantey JR, Pittman FE. Partial Purification of a Toxin Found in Hamsters with Antibiotic-Associated Colitis: Reversible binding of the Toxin by Cholestyramine. Gastroenterology 1978; 74: 1046.
- 18. Katz L, Lamont JT, Trier JS, Sonnenblick EB, Rothman SW, Broitman SA et al. Experimental Clindamycin-Associated Colitis in Rabbits: Evidence of Toxin-Mediated Mucosal Damage. Gastroenterology 1978; 74(2 Pt 1): 246-52.
- 19. Kay R, Dubois RE. Clindamycin/primaquine therapy and secondary prophylaxis against Pneumocystis carinii pneumonia in patients with AIDS. South Med J 1990; 83 (4): 403-4.
- 20. Kays MB, White RL, Gatti G, Gambertoglio JG: Ex vivo protein binding of clindamycin in sera with normal and elevated alpha1-acid glycoprotein concentrations. Pharmacotherapy 1992;12(1):50-55.
- 21. Keighley MR, Burdon DW, Arabi Y, Williams JA, Thompson H, Young D, Johnson M, Bentley S, George RH and Mogg GAG. Randomized Controlled Trial of Vancomycin for Pseudomembranous Colitis and Post-operative Diarrhea. BMJ 1978; 2 (6153): 1667-69.
- 22. LaMont JT, Sonnenblick EB, Rothman S. Role of Clostridial Toxin in the Pathogenesis of Clindamycin Colitis in Rabbits. Gastroenterology 1979; 76:356-61.
- 23. Larsen JW, Gabel-Hughes K, Kreter B. Efficacy and Tolerability of imipenem-cilastatin versus clindamycin + gentamicin for serious pelvic infections. Clin Ther 1992; 14(1): 90-6.
- 24. LeFrock JL, Prince RA, Klainer AS, Gainer RB, Kalis P. Parenteral clindamycin in the treatment of aerobic, anaerobic, and mixed anaerobic-aerobic infections. Cur Ther Res 1977; 21 (3): 289-314.
- 25. Levison ME, Mangura CT, Lorber B, Abrutyn E, Pesanti EL, Levy RS, MacGregor RR, Schwartz AR.Clindamycin compared with penicillin for the treatment of anaerobic lung abscess. Ann Intern Med 1983; 98: 466-71.
- 26. Martens MG, Faro S, Hammill HA, Smith D, Riddle G, Maccato M. Ampicillin/sulbactam versus clindamycin in the treatment of postpartum endomyometritis. South Med J 1990; 83 (4): 408-13.
- 27. Metzler CM, DeHaan R, Schellenberg D, VandenBosch W. Clindamycin Dose-bioavailability Relationships. J Pharm Sci 1973; 62: 591-98.
- 28. Moore FA, Moore EE, Mill MR. Preoperative antibiotics for abdominal gunshot wounds. Am J Surg 1983; 146: 762-5.
- 29. Ruf B, Pohle HD. Role of clindamycin in the treatment of acute toxoplasmosis of the central nervous system. Eur J Clin Microbiol Infect Dis 1991; 10: 183-6.
- 30. Safrin S, Finkelstein DM, Feinberg J, Frame P, Simpson G, Wu A, Cheung T, Soeiro R, Hojczyk P, Black JR. Comparison of three regimens for treatment of mild to moderate Pneumocystis carinii pneumonia in patients with AIDS. Ann Intern Med 1996;124(9):792-802.
- 31. Schumer W, Nichols RL, Miller B, Samet ET, McDonald GO. Clindamycin in the treatment of soft-tissue infections. Arch Surg 1973: 106: 578-81.
- 32. Tedesco F, Markham R, Furwith M, Christie D, Bartlett JG. Oral Vancomycin for Antibiotic-Associated Pseudomembranous Colitis. Lancet 1978; 2: 226-28.
- 33. Toma E. Clindamycin/primaquine for treatment of Pneumocystis carinii pneumonia in AIDS. Eur J Clin Microbiol Infect Dis 1991; 10: 210-3.
- 34. Toma E, Fournier S, Dumont M, Bolduc P, Deschamps H. Clindamycin/primaquine versus trimethoprim-sulfamethoxazole as primary therapy for Pneumocystis carinii pneumonia in AIDS: A randomized, double-blind pilot trial. Clin Inf Dis 1993;17:178-84.
- 35. Wynalda MA, Hutzler JM, Koets, MD, Podoll T, Wienkers LC: In vitro metabolism of clindamycin in human liver and intestinal microsomes. Drug Meta Dispos 2003;31:878-887.
- 36. Pfizer Canada Inc., Dalacin C Phosphate Sterile Solution Product Monograph, Control Number: 202620, Date of Revision: May 30, 2017.