


Product Monograph - Desmopressin Tablets
SUMMARY PRODUCT INFORMATION
Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Oral | Tablet 0.1 mg , 0.2 mg | Lactose, Potato Starch, Povidone, Magnesium Stearate For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Desmopressin Tablets is indicated for:
- treatment of Central Diabetes Insipidus
- treatment of Nocturnal Enuresis
Central Diabetes Insipidus
Desmopressin Tablets (0.1 and 0.2 mg desmopressin acetate) are indicated for the management of vasopressin sensitive central diabetes insipidus, and for the control of temporary polyuria and polydipsia following head trauma, hypophysectomy or surgery in the pituitary region.
Nocturnal Enuresis
Desmopressin Tablets (0.1 and 0.2 mg desmopressin acetate) are indicated in the management of nocturnal enuresis in patients 5 years of age and older who have normal ability to concentrate urine. Desmopressin Tablets should be used in conjunction with non-medicinal therapy, such as motivational counselling and bladder exercises.
CONTRAINDICATIONS
Hypersensitivity to desmopressin acetate or any of the tablet’s constituents. Because of the risk of platelet aggregation and thrombocytopenia, the drug should not be used in patients with type IIB or platelet-type (pseudo) von Willebrand’s disease.
Known hyponatremia, severe liver disease, nephrosis or any other condition associated with impaired water excretion, cardiac insufficiency, chronic renal insufficiency, congestive heart failure, habitual or psychogenic polydypsia.
Patients with existing medical conditions, which lead to sodium losing states such as nausea, bulimia, anorexia nervosa, chronic vomiting, diarrhoea and adrenocortical insufficiency as well as salt losing nephropathies, should only be prescribed DESMOPRESSIN TABLETS under close medical supervision and with extreme caution.
WARNINGS AND PRECAUTIONS
General
In general, by adequate treatment with Desmopressin Tablets, thirst is automatically reduced. However, there is potential risk of water intoxication, if during treatment, excessive liquid is consumed. It is advisable that patients, and especially the parents of child patients, be cautioned about this.
In patients with water and/or electrolyte balance disorder [such as systemic infections, fever, and Syndrome of Inappropriate Antidiuretic Hormone secretion (SIADH)], and in patients with high intra-cranial pressure, it is also necessary that extra care be exercised with liquid intake.
Desmopressin acetate is not effective in controlling polyuria caused by renal disease, nephrogenic diabetes insipidus, psychogenic diabetes insipidus, hypokalemia or hypercalcemia.
Fluid intake should be adjusted to reduce the possibility of water intoxication and hyponatremia especially in the very young and elderly patients (See Dosage and Administration). Particular attention should be paid to the risk of an extreme decrease in plasma osmolality and resulting seizures in young children.
Intranasal formulation of desmopressin acetate at high dosage (40 Fg or more) has occasionally produced a slight elevation of blood pressure, which disappeared with a reduction in dosage. The drug should be used with caution in patients with coronary artery insufficiency and/or hypertensive cardiovascular disease because of possible tachycardia and changes in blood pressure.
Lack of therapeutic response to oral desmopressin may be noted in some patients even at the maximum recommended dosage. These patients should be switched to the intranasal or injectable dosage form of desmopressin.
In the control of diabetes insipidus, the lowest effective dose should be used and the effective dosage, as determined by urine volume and osmolality and in some cases, plasma osmolality, should be assessed periodically.
Desmopressin should not be administered to dehydrated patients until water balance has been adequately restored.
Desmopressin should be used with caution in patients with cystic fibrosis because these patients are prone to hyponatremia.
Children and geriatric patients should be closely observed for possible water retention due to over ingestion of fluids. When fluid intake is not excessive, there is little danger of water intoxication and hyponatremia. Fluid intake should be carefully adjusted to prevent overhydration.
There are reports of changes in response over time, usually when the drug has been administered for periods longer than 6 months. Some patients may show decreased responsiveness, others a shortened duration of effect. There is no evidence that this effect is due to the development of binding antibodies, but may be due to local inactivation of the peptide.
Special Populations
Pregnant Women
Reproductive studies performed in rats and rabbits have revealed no evidence of harm to fetus by desmopressin. The use of desmopressin acetate in pregnant women with no harm to the fetus has been reported.
No controlled studies in pregnant women have been carried out. However, as with all medication used during pregnancy, the physician should weigh possible therapeutic advantages against potential risks in each case.
Nursing Women
There have been no controlled studies in nursing mothers. A single study on a post-partum woman demonstrated a marked change in maternal plasma desmopressin acetate level following an intranasal dose of 10 Fg, but little desmopressin was detectable in breast milk.
Pediatric Use
Desmopressin acetate has been used in children with diabetes insipidus. The dose must be individually adjusted to the patient with attention in the very young to the danger of an extreme decrease of plasma osmolality with resulting convulsions. Dosage in infants younger than 3 months has not been established. Dose should start at 100 Fg or less. Use of desmopressin acetate in infants and children will require careful fluid intake restriction to prevent possible hyponatremia and water intoxication.
Monitoring and Laboratory Tests
Diagnosis of Central Diabetes Insipidus
Central diabetes insipidus may be demonstrated by the inability to produce urine of osmolality above 175 mOsm/kg with dehydration severe enough to cause a loss of greater than 2% of body weight.
Patients are selected for therapy by establishing a diagnosis by means of a water deprivation test, the hypertonic saline infusion test, and/or response to 5 units arginine vasopressin given s.c. after dehydration. Continued response to desmopressin acetate is monitored by urine volume and osmolality. In cases of severe dehydration, plasma osmolality determination may be required.
ADVERSE REACTIONS
Infrequently, high doses of desmopressin have produced transient headache and nausea. Nasal congestion, rhinitis, flushing, and mild abdominal cramps have been reported. These symptoms disappeared with reduction in dosage.
Side effects reported from controlled clinical trials involving 638 subjects included headache (2%), and rhinitis (1%), nasal discomfort (1%), epistaxis (1%) and abdominal pain (1%). Other effects, reported at a frequency of less than 1% included dizziness, chills, wheezing, rash, edema of face and hands, nausea, constipation, anorexia, increased appetite, conjunctivitis and after taste in the mouth. These symptoms disappeared with reduction of dosage or withdrawal of drug. Adverse effects rarely necessitate discontinuance of the drug.
Serum SGOT levels were elevated in 4/16 patients 6 months after commencing oral desmopressin acetate therapy (200 to 600 Fg/day). Two of these patients had exhibited baseline levels of SGOT that were above the normal range and all four patients had normal SGOT levels on repeat test at 9 months, even though desmopressin acetate administration continued. The possibility that desmopressin acetate has an adverse effect on serum enzymes is therefore remote.
DRUG INTERACTIONS
Clofibrate, chlorpropamide and carbamazapine may potentiate the antidiuretic activity of desmopressin while demeclocycline, lithium and norepinephrine may decrease its activity.
Although the pressor activity of desmopressin acetate is very low compared with the anti-diuretic activity, use of large doses of desmopressin with other pressor agents should be done only with careful patient monitoring.
Concomitant treatment with drugs which are known to induce SIADH, e.g. tricyclic
antidepressants, selective serotonine reuptake inhibitors, chlorpromazine and carbamazepine, may cause an additive antidiuretic effect leading to an increased risk of water intoxication.
Concomitant use of non-steroidal anti-inflammatory drugs (NSAIDs) including Cox-2 inhibitors such as Celebrex® may induce water retention and hyponatremia.
Concomitant treatment with opiates such as loperamide may result in a 3-fold increase of plasma desmopressin concentrations, which may lead to water retention and hyponatremia. Although not investigated, other drugs slowing intestinal transport might have the same effect.
Intake of a standardised meal with oral desmopressin resulted in significant decreased bioavailability compared to fasting. This is hypothesised to be due to reduced absorption from the gastrointestinal tract. However no effect on dynamics (urine production or osmolality) was observed.
DOSAGE AND ADMINISTRATION
Central Diabetes Insipidus
Desmopressin Tablets dosage must be determined for each patient and adjusted according to the pattern of response. Response should be estimated by adequate duration of sleep and adequate, not excessive, water turnover and maintenance of urine osmolality at levels of 400 mOsmol/kg or greater.
To institute desmopressin therapy, patients should be withdrawn from previous medication and allowed to establish a baseline polyuria and polydipsia. The stable polyuria is used as a baseline to determine the magnitude and duration of the response to medication. In less severe cases, prior water loading may be desirable to establish a vigorous flow of urine. When the urine osmolality reaches a plateau at the low level (in most cases, less than 100 mOsm/kg), the first oral dose (eg., 100 Fg) of desmopressin is administered. A urine sample is obtained after two hours and hourly thereafter; urine volume is measured and urine osmolality determined. When the patient has reached the previous baseline urine osmolality and urine flow, the drug effect has ceased and the next desmopressin dose is administered. The cycle is then repeated until the patient has reached a stable condition.
Dosage must be individualized. A suitable starting dose for adults and children is 100 Fg (0.1 mg desmopressin acetate) three times daily. This dosage regimen should then be adjusted in accordance with the patient's response in order to ensure an optimum dose. For patients who have been controlled on intranasal desmopressin and who are to be switched to the oral form, the oral dose producing comparable antidiuresis is about 10-20 times greater than the established intranasal dose. Geriatric patients may be more sensitive to the antidiuretic effect of the usual adult dose of desmopressin acetate.
In children, the evening dose is usually 2x higher than the morning and midday dose to ensure sufficient antidiuresis during sleep. This is generally not a requirement for adult patients, presumably because adults sleep for shorter periods of time.
The maximum recommended dosage for both adults and children is 1.2 mg per day (400 Fg t.i.d.). Although there is no evidence that potentially serious adverse reactions would occur at daily doses greater than 1.2 mg, a maximum of 1.2 mg is being recommended at the present time since clinical experiences with daily dosages exceeding 1.2 mg is limited. The lowest effective dosage should be given. Rarely, during long term use, patients may develop tolerance to the drug and require cautious increase in dosage to achieve adequate therapeutic response.
Primary Nocturnal Enuresis
The dosage of Desmopressin Tablets must be determined for each individual patient and adjusted according to response. Patients previously on intranasal desmopressin acetate therapy can begin tablet therapy the night following (24 hours after) the last intranasal dose. The recommended initial dose is 0.2 mg 1 hour before bedtime. The dose may be titrated up to 0.6 mg to achieve the desired response using the following dosage plan. If the patient experiences a wet night after three days on an initial dose of 0.2 mg (1 x 0.2 mg tablet), increase the dose by 0.2 mg. The dose may be increased by 0.2 mg increments, in the manner described (every 3 days), to a maximal dose of 0.6 mg. The physician should be consulted if enuresis persists at the maximal dose. A restricted fluid intake is recommended a few hours before administration, especially one hour before bedtime. As most children sleep between 8 to 12 hours, further restriction is not required. In the event that the child wakes up during the night, liquid intake should be restricted.
OVERDOSAGE
Overdose symptoms include headaches, abdominal cramps, nausea, and facial flushing. There is no known antidote. Dosage and frequency of administration should be reduced, or the drug withdrawn, according to severity of the condition.
Water retention can be controlled by decreasing the dosage of desmopressin; severe water retention caused by overdosage may be treated with a diuretic such as furosemide.
ACTION AND CLINICAL PHARMACOLOGY
Desmopressin acetate is a synthetic structural analogue of the antidiuretic hormone, arginine vasopressin, which alters the permeability of the renal tubule to increase resorption of water. The increase in the permeability of both the distal tubules and collecting ducts appears to be mediated by a stimulation of the adenylcyclase activity in the renal tubules.
Although the bioavailability of orally ingested desmopressin is low, reported as being about 1 to 5%, it is sufficient to induce an antidiuresis (urine osmolality greater than 400 mOsm/kg) lasting
7 to 9 hours in healthy subjects and in patients with diabetes insipidus. Recent clinical studies of the pharmacokinetics and pharmacodymamics of desmopressin showed that desmopressin has a longer antidiuretic action than previously reported. Plasma desmopressin concentrations from healthy volunteers were analysed using a new and sensitive bioassay with a low limit of quantification (LLOQ) of 0.8 ng/L. Desmopressin in-vivo potency was found to be 1.64 ng/L based on urine osmolality of 200 mOsm/kg. Given the high variability in absorption, the pharmacological antidiuretic effects of desmopressin can be expected to last from 6 hours up to 14 hours.
Onset of action, as determined by decreased urine volume and increased urine osmolality, is within one hour. In both adults and children, there is a log linear relationship between desmopressin acetate doses and maximal urine osmolality and duration of antidiuresis within the dose range 12.5 to 400 Fg. Measurements of plasma desmopressin concentrations after peroral desmopressin acetate administration show a linear relationship between amounts of desmopressin acetate absorbed and dose, but with great interindividual differences.
Pharmacodynamics
Clinical studies have demonstrated that peroral administration of desmopressin acetate is active in eliciting an antidiuretic effects in humans, be they normal subjects, or adults and children suffering from central diabetes insipidus (CDI) of various etiologies, or from nocturnal enuresis. The synthetic analogue exhibits a greater antidiuretic potency, as well as a longer half-life and duration of action, as compared to endogenous antidiuretic hormone.
When administered as a solution (20-200 Fg per 50 mL water), desmopressin acetate produced a dose dependent effect both on the magnitude and the duration of the antidiuretic response as determined by measurements of urine osmolality, urine volume and free water clearance. Administration of desmopressin acetate through a duodenal tube caused similar antidiuretic effects, indicating that the intact peptide can be absorbed from the gastrointestinal mucosa. Onset of action was approximately 1 hour.
Figure 1
Urine osmolality (top panel), urine volume (mid panel) and free water clearance (lower panel) during 15 minute periods in hydrated human volunteers following peroral administration of 20, 40 and 200 Fg of desmopressin acetate. Mean ± SEM, N = 5 for each dose.
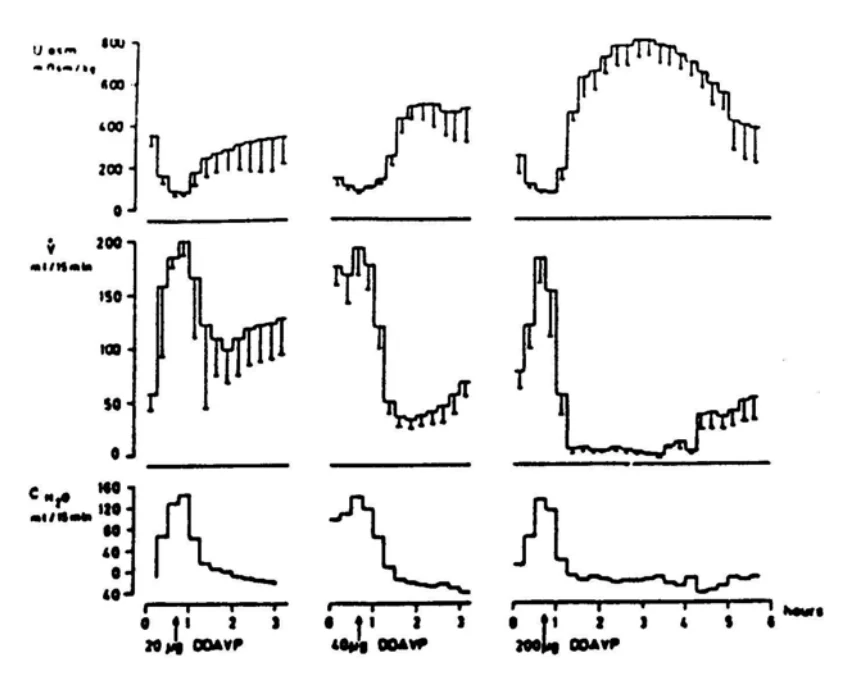
The effect of desmopressin acetate tablets was similar to that of the desmopressin solution but with an apparently slightly longer duration of action; each patient required a slightly different daily regimen for satisfactory control of water balance. The average daily PO dose, 300 Fg (range of 200 - 350 Fg), was 11x that of the mean previous intranasal dose (27 Fg, range of 10 to 40 Fg), with dosing frequency being more often t.i.d. (in 8/9 patients) rather than the more usual b.i.d. intranasal regimen.
Urine osmolality increased rapidly during the second hour and in a similar manner following either intranasal doses of 10 or 20 Fg or peroral doses of 200 or 400 Fg desmopressin acetate. The onset of action tends to coincide with the appearance of desmopressin in the plasma (15 min) and plasma levels, which reached maximal values 1-2 hours after 100-200 Fg desmopressin acetate was administered orally, remained fairly constant over the six-hour observation period.
There are no differences in terms of magnitude and duration of the response between the two routes of administration, with free water clearance remaining negative for approximately 7 to 8 hours. When the criterion for a good antidiuretic effect was set at a urine osmolality of greater
than 400 mOsmol/kg, the mean (± SD) duration of the antidiuretic effect, in hours, was 7.4 ± 3.0 and 9.0 ± 3.2 after 10 and 20 Fg IN, respectively, and 7.2 ± 3.3 and 8.8 ± 2.3 after 200 and 400 Fg PO, respectively. Large interindividual differences in duration of the antidiuretic effect (i.e., 5-24 hours) following intranasal application of 20 Fg desmopressin acetate have also been reported in earlier studies.
The data recorded from urine volume and osmolality measurements showed no statistically significant difference between fasting and non-fasting healthy subjects in response to 100 and 200 Fg desmopressin acetate tablets; no effects on blood pressure 1 or 3 hours after desmopressin acetate administration were seen.
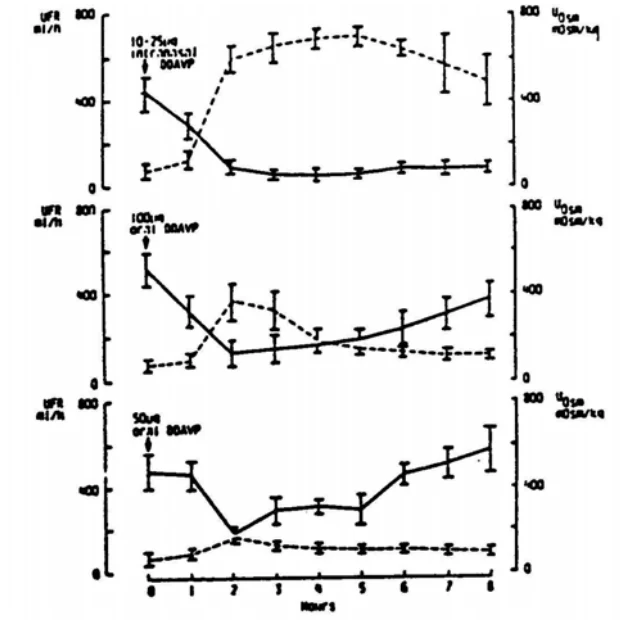
Intranasal desmopressin acetate (10-25 Fg) in children had a more marked and prolonged antidiuretic effect compared to the response obtained with 50 and 100 Fg oral doses in the same children. This difference is not surprising in view of the greater peptidase activity in GI secretions.
Desmopressin acetate does not directly affect urinary sodium or potassium excretion, or serum sodium, potassium, or creatinine concentrations. It does not stimulate uterine contractions, adrenocorticotropic hormone release or increase plasma cortisol concentrations.
Figure 2
Mean (±SEM) urine flow rate (solid lines)] and urinary osmolality (dotted lines) in four water-loaded children with CDI after 50 and 100 Fg oral desmopressin acetate and 10-25 Fg intranasal desmopressin acetate.
Pharmacokinetics
The results of pharmacokinetic studies conducted with oral desmopressin acetate are summarized in Table 1. The most striking feature of the pharmacokinetic data was the large intra- and interindividual differences noted in all of the studies.
Dose-response relationships and pharmacokinetic profile of orally administered desmopressin acetate were similar in normal subjects and in adults and children with CDI. In all studies, both the magnitude of the plasma peak concentration and the AUC were dose dependent. Time to peak plasma concentration and the plasma half-life were not affected by the size of the dose.
Table 1: Summary of Pharmacokinetic Parameters in Normal Subjects (NS) and Patients with Central Diabetes Insipidus (CDI). Numbers in brackets indicate the number of subject/patients from which the parameter was derived.
| Dose | AUC (ng/L.hr)(N) | Cmax (ng/L)N) | Tmax (min)(N) | T1/2 (hour)(N) | ||||||||||||
| (Fg) | ||||||||||||||||
| A | B | C | D | A | B | C | D | A | B | C | D | A | B | C | D | |
| 50.0 NS | 10.2 (2) | - | - | - | 1.9 (5) | 1.7 (5) | - | - | 96 (5) | 60 | - | - | 3.1 (2) | 1.4 (5) | - | - |
| 100. NS | 14.4 (5) | - | - | - | 3.6 (5) | 3.2 (5) | - | - | 96 (5) | 60 | - | - | 1.9 (5) | 1.9 (5) | - | - |
| 200. NS | 39.8 (3) | - | - | - | 7.1 (4) | 7.0 (4) | - | - | 90 (4) | 120 | - | - | 2.0 (3) | 2.4 (4) | - | - |
| 12.5 CDI | - | - | - | - | - | - | 3.5 (3) | - | - | - | 53 (3) | - | - | - | - | |
| 25 CDI | - | - | 15.1 (5) | - | - | - | 5.3 (5) | - | - | - | 96 (5) | - | - | - | 2.3 (5) | - |
| 50 CDI | - | - | 11.4 (2) | - | - | - | 7.3 (3) | - | - | - | 84 (3) | - | - | - | 2.3 (2) | - |
| 100 CDI | - | - | 25.9 (4) | - | - | - | 9.2 (4) | - | - | - | 53 (4) | - | - | - | 1.8 (4) | - |
| 200 CDI | 27.1 (5) | - | 129 (5) | 148 (7) | 7.8 (6) | 7 (7) | 34 (4) | 33 (7) | 70 (6) | 60 | 54 (5) | 48 (7) | 2.5 (5) | 2.1 (7) | 2.6 (5) | 3 (7) |
| 400 CDI | - | - | 162 (4) | 246 (7) | - | - | 56 (4) | 104 (7) | - | - | 50 (4) | 49 (7) | - | - | 1.9 (4) | 2.5 (7) |
Plasma desmopressin levels increased in a dose-dependent fashion and its disappearance from plasma followed an exponential time course, with half-life of 86 to 142 minutes. In contrast, the elimination of desmopressin after IV injection is biexponential with rapid first phase and slower second phase half-lives of 7.8 minutes and 75.5-103 minutes, respectively. Because of the great inter-individual differences, the dose-response curves of the different patients show different slopes.
Linear regression analysis suggests that the lowest dose of peroral desmopressin acetate having a biological effect is approximately 10 Fg and that a significant antidiuretic effect (i.e., urine volume less than 2 mL/min) would be obtained with a peroral desmopressin acetate dose of 40 Fg; doubling this dose would increase the duration of the antidiuresis approximately 4.5 hours. These results are in accordance with those reported by Moses et al. following SC administration of desmopressin acetate.
A graded renal response to desmopressin acetate seems to take place between plasma concentrations of 1 to 5 ng/L with maximal effect of desmopressin acetate on the water permeability of the collecting ducts being reached at plasma concentrations of 4-5 ng/L. To obtain an effective plasma concentration, an oral dose of at least 100 Fg will be needed in most cases.
Both the intranasal and oral routes of administration exhibited first order kinetics and the plasma half-life was not different after oral or intranasal dosing. The pharmacokinetic data obtained in a recent study in children are presented in Table 2.
Table 2: Pharmacokinetics of Typical Therapeutic Doses of Oral and Intranasal Desmopressin in CDI Patients
| Test | Unit | 10 Fg IN | 20 Fg IN | 200 Fg PO | 400 Fg PO |
| AUC (0-infinity) | ng/L/h | 135 ± 116 | 226 ± 187 | 148 ± 152 | 246 ± 367 |
| Cmax | ng/L | 41.4 ± 31.6 | 75.6 ± 70.3 | 33.2 ± 30.7 | 103.9 ± 176.4 |
| Tmax | min | 41 ± 23 | 39 ± 14 | 48 ± 21 | 49 ± 19 |
| t1/2 | hours | 2.52 ± 1.39 | 4.19 ± 2.84 | 2.96 ± 2.04 | 2.47 ± 2.92 |
| Kel | h-1 | 0.35 ± 0.16 | 0.23 ± 0.11 | 0.34 ± 0.22 | 0.47 ± 0.27 |
| Max osm | mOsm/kg | 756 ± 201 | 828 ± 198 | 733 ± 156 | 809 ± 77 |
| time to max osm | min | 253 ± 111 | 373 ± 126 | 315 ± 127 | 345 ± 77 |
The distribution of desmopressin has not been fully characterized. It is not known if desmopressin crosses the placenta. The drug may be distributed into milk. The metabolic fate of desmopressin is unknown. Unlike vasopressin, desmopressin apparently is not degraded by aminopeptidases or other peptidases that cleave oxytocin and endogenous vasopressin in the plasma during late pregnancy.
Urinary clearance in 6 hydrated volunteers was calculated to be 0.514 mL/min/kg body weight and the amount of peptide excreted in the urine during the 6-hour observation period constituted 16.4% of the amount absorbed from the intestine over the same period of time. Urinary clearance for desmopressin is thus smaller than that reported for vasopressin.
Comparisons of Routes of Administration
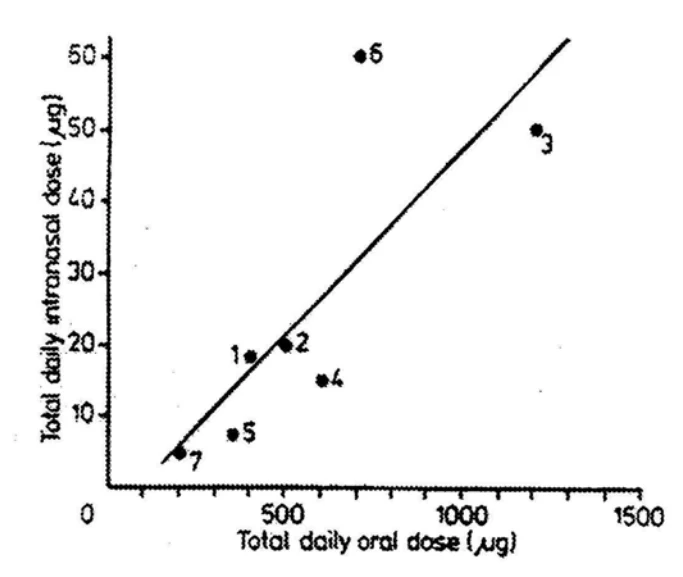
Peroral desmopressin acetate offers an effective alternative to intranasal administration in the treatment of central diabetes insipidus and nocturnal enuresis. In one study, five out of six patients with CDI of varying etiology who were effectively treated with intranasal desmopressin acetate therapy (mean daily dose = 37 Fg, range: 15-75 Fg) were well-controlled with mean daily doses of 345 Fg desmopressin acetate PO (range: 75-900 Fg). The ratio of PO/IN dose was therefore approximately 10 in this study. As with intranasal application, patient dosage requirements varied and a dose range rather than a standard dose is usually necessary to control diabetes insipidus in a given patient population. However, a significant (p<0.01) correlation between the previous intranasal dose and the effective oral daily dose can generally be established both in adults (Fig. 3) and children (Fig. 4).
Other long term studies of 6 to 18 months duration have variously reported IN/PO dose ratios as being 1:14, 1:15, 1:20, and 1:40. In CDI patients, the intranasal dose was 25x greater than an equipotent intravenous dose and the peroral dose is approximately 10 to 20x the previous 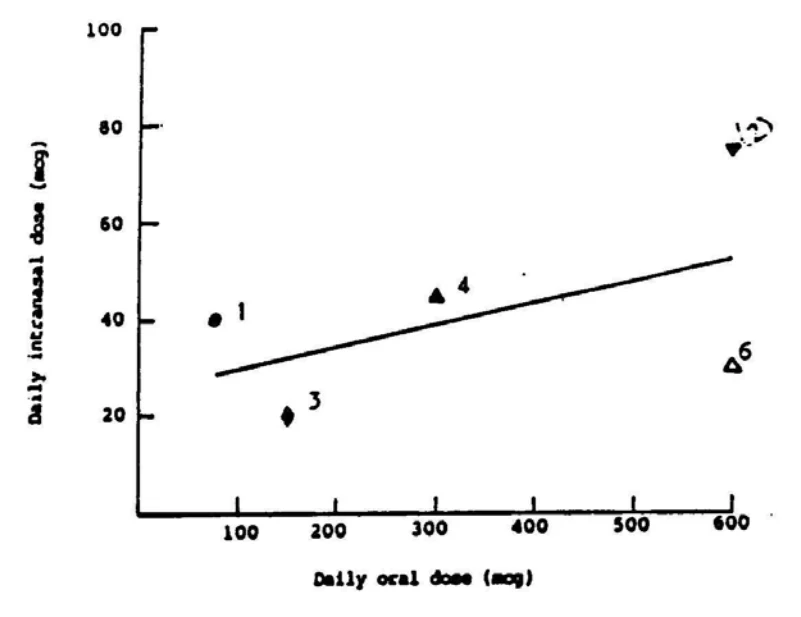
intranasal dose. Thus, the ratio between equipotent doses of IV, IN and PO administered desmopressin acetate seems to be, in general, 1:25:300.
Figure 3
Relationship between intranasal and oral dosing were seen with any of the desmopressin doses administered.
Figure 4
Correlation between intranasal and oral doses of desmopressin acetate in seven pediatric cases. Coefficient of correlation r = 0.79 (p<0.01).
In a recently conducted study, healthy subjects were water loaded to suppress endogenous vasopressin levels. The aim of the study was to investigate the antidiuretic effectiveness of five low doses of desmopressin and placebo. Due to wide inter- and intra-individual variations seen with the oral route, an intravenous infusion study was designed to minimize the variations. The study provided information about the pharmacokinetic and pharmacodynamic (PK/PD) relationship of low doses of desmopressin levels and their duration of anti-diuretic action. Combining this new insight into the correlation between plasma desmopressin levels and anti-diuretic effects of desmopressin with plasma concentration-time profiles after oral administration of desmopressin, showed that desmopressin is a potent compound with EC50 value of 1.6 ng/L. Thus desmopressin can be expected to have a continued effect even at a very low plasma level of 1 ng/L. After oral administration, an effect lasting from 6 to 14 hours can be expected.
Seventy two over-hydrated non smoking male subjects participated in a phase I study investigating the antidiuretic effect and pharmacokinetics of 30, 60, 125, 250 and 500 ng desmopressin and placebo infused intravenously at a constant rate for two hours. A clear positive dose-response slope was seen between duration of anti-diuretic action (primary endpoint) and dose of desmopressin (placebo included as zero), independent of the cut-off level (either 200 mOsm/kg or 400 mOsm/kg. No placebo response was seen, and very limited response was seen with 30 ng desmopressin. An increase in duration of antidiuretic action (DOA) with increasing dose of desmopressin was statistically significant for most pairwise comparisons. In the 250 ng
and 500 ng desmopressin groups the median duration of anti-diuretic action was 5.36 hours (range: 0.75-10.64 hours) and 8.00 hours (range: 4.45-11.66 hours), respectively, when using 200 mOsm/kg as cut-off, while it was 3.94 hours (range: 0-7.56 hours) and 6.27 hours (range: 4.35-8.28 hours), respectively, when using 400 mOsm/kg as cut-off. The dose-response curve for the DOA did not flatten out within the dose range of 0-500 ng desmopressin for either cut-off (200 or 400 mOsm/kg), i.e. the plateau of the curve was not observed. This indicates that further increase in dosage (>500 ng) may increase duration of anti-diuretic action. Linear relationship between DOA and log (dose) among the dose range of 30-500 ng desmopressin was observed independent of cut-off level (either 200mOsm/kg or 400mOsm/kg).
No serious adverse events were seen with any of the desmopressin doses administered.
The analysis of other pharmacodynamic endpoints (maximum osmolality, AUC 0-6 hour for osmolality, AUC 0-6 hour for absolute change from dosing in osmolality) showed a clear positive dose-response relationship. The median maximum osmolality in the placebo group was 80 mOsm/kg (range: 55-183 mOsm/kg), while median maximum osmolality was 830 mOsm/kg (range: 762-1052 mOsm/kg) in the 500 ng desmopressin group.
Twenty-eight non-smoking healthy (n=14 male and n=14 female) subjects took part in a single-centre, open-labelled, randomised, study investigating the antidiuretic effect and pharmacokinetics of a 400 µg dose of desmopressin, taken as two of the currently marketed 200 µg tablets. Blood samples for plasma concentrations of desmopressin were collected according to the following schedule: pre-dose (i.e. 0-30 minutes pre-dosing), 15, 30 min 1, 1.5, 2, 3, 4, 6, 8, 9, 10, 11, 12, 13 and 14 hours after dosing. The concentration of desmopressin in plasma was determined by a validated RIA method. The lower limit of quantification (LLOQ) of the assay was 0.8 ng/L. After administration of Desmopressin Tablets, the geometric mean tmax was observed at 1.0 hour after dosing, the geometric mean value for C max was 20.8 (CV =60%) ng/L, the geometric mean value for AUC t was 71.8 (CV=57%) (hr.ng/L), and the geometric value for AUC was 77.2 (CV=55%) (hr.ng/L).
Sixty four percent (64%) of the subjects had plasma desmopressin concentration above 1 ng/L at 12 hours post dose. No safety concerns were observed.
Pediatric Considerations:
As was the case with adults, peroral desmopressin acetate proved to be as effective as the intranasal administration of desmopressin acetate and was preferred by the patients. The pharmacodynamic activity is also similar. Doses as small as 12.5 Fg have an effect on diuresis and urine osmolality but therapeutic doses start at above 100 Fg; 200 Fg peroral desmopressin
acetate produces antidiuresis varying from 8 to 12.5 hr. As with adults, more frequent oral administration (t.i.d. vs. b.i.d.) often resulted in a better clinical response.
Bioavailability
Any cleavage of peptide bonds or reduction of the disulfide bridge of desmopressin leads to biological inactivation. The antidiuretic effect observed after peroral administration indicates that the desmopressin molecule is absorbed into the systemic circulation in intact chemical form.
Transmucosal absorption of the peptide takes place over a considerable period of time. Using a value of 2.2 mL/min/kg body weight for the metabolic clearance of desmopressin obtained during infusion of desmopressin acetate in humans, it was calculated that the bioavailability of desmopressin acetate during the first 6 hours after administration of the drug was 11.3% for the intranasal route as compared to 1.0 and 0.7% for the oral route at doses of 100 and 200 Fg respectively. This value is lower than that calculated for children in which the relative bioavailability of the oral route of administration compared to the intranasal route was found to be approximately 5%.
STORAGE AND STABILITY
Desmopressin Tablets should be stored between 15EC -25EC in a dry place.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Desmopressin Tablets are available as white uncoated tablets containing 0.1 mg or 0.2 mg of desmopressin acetate, supplied in bottles of 7, 30 or 100 tablets.
OH
CH2
CH
O
C
CH CH2 NH
C O
NH NH
NH C
O CH2
CH
O C NH2
C
O
NH
O
C
CH2
CH2
S
CH2
S
CH
O
C
CH CH2 CH2 C NH2
O
N
CH2
CH2 CH2
CH C
O
NH CH
CH2
CH2
CH2
NH
C NH
NH2
CH3COOH 3H2O C
O
C
O NH CH2 NH2 PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Desmopressin Acetate
Chemical names: 1-Desamino-8-D-arginine vasopressin acetate trihydrate
1-(3-mercaptopropionic acid)-8-D-arginine vasopressin monoacetate (salt) trihydrate
Molecular formula and molecular mass:
C48H74N14017S2 (acetate trihydrate)
MW = 1183.2
C46H64N14O12S2 (free base)
MW = 1069.2
Structural formula:
Physicochemical properties:
Desmopressin acetate is a white lyophilized powder which is soluble in water, methanol, ethanol, and acetic acid, and sparingly soluable in chloroform and ethyl acetate. An aqueous solution of 1 mg/mL at 24EC has a pH of 4.8.
CLINICAL TRIALS
Six patients aged 23 to 65 years took part in an open dose-ranging study of desmopressin acetate tablets followed by a four week open study on an out-patient basis. All patients completed the dose range study in hospital and were discharged on a dosage regimen ranging from 25 to 200 Fg t.i.d.
A dose-dependent effect was seen at doses of 12.5, 25, 50, 100 and 200 Fg desmopressin acetate both for duration and magnitude of antidiuretic activity. All doses elicited an antidiuretic response although doses of 100 to 200 Fg induced a more optimum duration of antidiuretic activity. Although there were large interindividual differences, most patients were stabilized on a mean daily dose of 345 Fg desmopressin acetate (range 75 to 900 Fg). One patient dropped out of the study due to inadequate response to oral therapy, despite being treated with 400 Fg t.i.d. This patient had been previously well controlled with a dosage of 10 Fg t.i.d., intranasally. The individual response varied greatly between patients in both magnitude and duration but was found to be of the same order of magnitude as for intranasal desmopressin acetate which had previously been administered in daily doses of 15 to 75 Fg in these patients.
No adverse reactions were reported. No significant deviations from normal laboratory values for hematology, blood chemistry including liver function, serum electrolytes or urinalysis were noted, and there were no clinically important changes in body weight or blood pressure. Two patients who received cortisone had lower baseline diuresis than other patients and required a lower desmopressin acetate dose to control adequate water turnover. However, neither cortisone nor thyroxine interfered with desmopressin acetate efficacy.
Six patients aged 21 to 59 years completed 18 months of oral desmopressin acetate therapy and 4 patients had completed 6 to 12 months of therapy. These patients were well controlled with satisfactory water turnover at doses within the range of 100-200 Fg t.i.d., with no development of tolerance to desmopressin acetate.
No adverse reactions were reported that could be related to desmopressin acetate therapy. One patient was withdrawn at 6 months after tests revealed recovery from diabetes insipidus. Four patients showed elevated serum SGOT levels at 6 months which, however, were normal on repeated testing at 9 month follow-up. Two patients experienced elevated alkaline phosphatase values. One of these patients had elevated levels at baseline. Elevated alkaline phosphatase levels are quite normal during growth and the 2 patients showing elevated baseline levels were 5
and 15 years old. None of the minor changes noted in serum total protein, electrolytes (Na, K, C1) or glucose or in the plasma osmolality were considered to be of any clinical significance. There were no clinically significant changes in blood pressure or body weight.
Two trials investigated the long-term efficacy and safety of Desmopressin Tablets for primary nocturnal enuresis. The first study continued for six months. One hundred and twenty-five (of the 232 enrolled) completed the trial; 92 were male, 33 were female. Patients were 6-17 years of age with a mean age of 9.34. All patients were assigned to a dose of 200 Fg for two weeks. The dose was increased in increments of 200 Fg every two weeks until the patient was completely dry (over a 14-day period) or had reached a maximum dose of 600 Fg. The data obtained in this trial indicate that desmopressin 200 Fg reduces the mean number of wet nights within two weeks and sustains this effect over a six-month treatment period. The safety profile was unremarkable. The number of patients who reported one or more adverse events was: 200 Fg dose - 57 (25%); 400 Fg dose - 54 (24%), and 600 Fg dose - 44 (47%). Headache, pharyngitis, rhinitis and infection were the most commonly reported adverse events.
The second (Canadian) trial investigated the long-term safety of oral desmopressin treatment for up to one year, in children with nocturnal enuresis. Two hundred and fifty-six patients were treated with desmopressin; 80% of these patients were male with a mean age of 9.6 years (range 6-18 years). Of the 80 children completing the trial, 27 became dry (at most one wet night) for at least 28 days. Of the 24 adverse events evaluated as possibly/probably related to treatment, 16 were evaluated as mild, seven were moderate [nausea (1), headache (3), mood swings (2), bacterial infection (1)], and one was severe (vomiting).
TOXICOLOGY
(i) Acute Toxicity
The IV acute toxicity of desmopressin acetate is very low. Mice tolerate IV doses of 2 mg/kg (Table 3). At doses of 30 Fg/kg in rats and 50 Fg/kg in rabbits, only transient changes in clinical behaviour were observed. Intravenous doses up to 24 Fg/kg in dogs did not produce any cardiovascular changes.
Table 3: Acute Toxicity of Desmopressin Acetate
| Species | Number | LD50 Dose | Route |
| Mice | 10, both sexes | 2 mg/kg | IV |
| Rats | 12, both sexes | 30 Fg/kg | IV |
| Rabbits | 6, both sexes | 50 Fg/kg | IV |
| Dogs | 5, males | 24 Fg/kg | IV |
(ii) Subacute Toxicity
Results from 14-day studies show that the drug given intravenously to rats at 18 Fg/kg/day and to rabbits at 6 Fg/kg/day caused no biologically significant changes in hematological and clinical chemistry parameters. Post-mortem examinations did not reveal any abnormalities.
Rats which received 5 mg/kg/day SC for 3 weeks did not show any significant changes in weight, blood count, or organ changes.
(iii) Chronic Toxicity
Subcutaneous Administration - Rat Studies
Rats (20 per group) which received doses of 5, 50 and 500 ng/kg/day, for six months did not show any significant changes in weight, blood values, or levels of transaminases. The weight of heart, lungs and kidneys decreased in female animals in the lower dose groups but not in the higher ones. In the male animals a decrease in non-esterified fatty acids was noted.
Dog Studies
Dogs (3 per group) which received SC doses of 10 and 100 ng/kg/day for 6 months did not show any significant changes in comparison with control groups in blood sugar or transaminases and did not show histological or morphological organ changes.
Oral Administration
Rat Studies
Oral administration of desmopressin to rats (20 male and 20 females per group dosed at 25, 75 and 200 Fg/kg/day) did not reveal any clinical findings related to desmopressin. Treated male and female rats were comparable to controls with respect to food consumption, body weight gain and water consumption. There were no drug-induced ocular abnormalities.
A dosage-related reduction was seen in levels of total circulating white blood cells, attributable to reduced neutrophil and lymphocyte counts in treated females, when compared with controls, at the week 13 and 26 investigations. Treated males were not affected.
Reduced plasma Factor VIII levels were seen in treated females at week 14 and treated males at week 25 in comparison with controls.
The terminal studies revealed no morphological or histological changes related to treatment with desmopressin.
Dog Studies
When desmopressin was given orally to dogs (4 males and 4 females per group, at 0, 25, 75 and 200 Fg/kg/day) all animals survived the 26-week period and no clinical signs were observed that were related to treatment. There were no adverse effects on body weight, food and water consumption and no ocular abnormalities. Hematological investigations revealed no treatment-related findings.
During weeks 6, 13 and 26 serum total protein concentrations of treated animals were increased due to an increase in the globulin fraction. However, there were no changes from the pre-dose values in males at 200 Fg/kg/day after 13 and 26 weeks treatment and males at 75 Fg/kg/day after 26 weeks treatment.
No organ morphological or histological changes were seen on autopsy which could be related to treatment with desmopressin.
Reproduction Studies
In a teratogenicity study in Wistar rats, neither teratologic nor embryotoxic effects were observed in 369 fetuses from 40 females dosed with up to 50 ng/kg/day desmopressin acetate SC during day 1 to day 20 of gestation.
In a study of 78 Dutch belted rabbits which received SC doses of desmopressin acetate up to 10 Fg/kg/day during the sixth and eighteenth day of pregnancy, neither teratogenic nor embryotoxic effects were observed in 296 fetuses. Weaning was unaffected.
REFERENCES FOR DIABETES INSIPIDUS
- 1.
Besser GM, Cunnah D. A Clinical Trial with Peroral administration of DDAVP
(desmopressin acetate) tablets in the treatment of Central Diabetes Insipidus.-A long Term Study in Outpatients. Data of File at Ferring Inc.,1986.
- 2.
Burrow GN, Wassenaar W, Robertson GL, Sehl H. DDAVP treatment of Diabetes
Insipidus during pregnancy and the post-partum period. Acta Endocrinologica 1981; 97:
23.
- 3. Chau R. Acute intravenous toxicity of DDAVP in rats. Data on File at Fering Inc., 1982
- 4.
Chau R. Acute intravenous toxicity of DDAVP in rabbits. Data on File at Fering Inc.,
1982
- 5.
Chau R. Fourteen-day intravenous safety study of DDAVP in rats. Data on File at
Fering Inc., 1982
- 6.
Chau R. Fourteen-day intravenous safety study of DDAVP in rabbits. Data on File at
Fering Inc., 1982
- 7.
Cort JH. Acute cardiological toxicity of ampouled desmopressin acetate. Data on File at
Fering Inc., 1978.
- 8. Cunnah D. Ross G, Besser GM. Management of cranial diabetes insipidus with oral desmopressin (DDAVP). Clin Endocrinol 1986; 24: 253-257.
- 9. Edwards CRW, Kitau MJ, Chard T, Besser GM. Vasopressin analogue DDAVP in diabetes insipidus: Clinical and laboratory studies. Brit Med J 1973; 2: 375-378.
- 10. A pharmacokinetic study of peroral administration of DDAVP given as tablets in doses from 12.5 to 400 µg. Ferring data, 14 January 1987.
- 11. A pharmacokinetic study of peroral administration of desmopressin (DDAVP) given as tablets in doses from 50 to 200 µg. Ferring data, 14 January 1987.
- 12.
Fjellestad A, Czernichow P. Central diabetes insipidus in children. Acta Paediatr Scand
1986; 75: 605-610.
- 13.
Fjellestad A, Tubiana N, Harris A, Czernichow P. Central diabetes insipidus in children:
Antidiuretic effect and pharmacokinetics of intranasal and peroral DDAVP. Acta Endocrinologica (Copenh) 1987,115: 307-312.
- 14. Green OP, Heaps CJ. DDAVP toxicity to rats by repeated oral administration for 26 weeks. Data on File at Ferring Inc., 1986.
- 15. Hammer M. A clinical trial of peroral administration of DDAVP in the treatment of central diabetes insipidus.A long term study (18 months) in outpatients. Data on file at Ferring Inc., 1986.
- 16. Hammer M, Vilhardt H. Peroral treatment of diabetes insipidus with a polypeptide hormone analog, desmopressin. J. Pharm Exp Ther 1987; 234 (3):754.
- 17. Harling RJ, Chesterman H, Spencer-Briggs DJ, et al. DDAVP oral toxicity study in beagle dogs. Data on File at ferring Inc., 1986.
- 18.
Rittig S, Jensen AR, Jensen KT, Pedersen EB. Effect of food intake on the
pharmacokinetics and antidiuretic activity of oral desmopressin (DDAVP) in hydrated normal subjects. Clin Endocrinol (Oxf) 1998 Feb, Vol: 48 (2) 235-41.
- 19. Moses AM, Moses LK, Nostman DD, Springer J. Antidiuretic responses to injected desmopressin, alone and with indomethacin. J Clin Endocrinol Metab 1981; 52: 910-913.
- 20. Nilsson A, Hedner P. A clinical trial with peroral administration of DDAVP Tablets in the treatment of central diabetes insipidus in adults.Data on File at Ferring Inc., 1986.
- 21. Pullan PT, Burger HG, Johnston CI. Pharmacokinetics of DDAVP in patients with central diabetes insipidus. Clin Endocrinol 1978; 9: 273-278.
- 22. Rado JP, Marosi J, Fischer J. Comparison of the antidiuretic effect of single intravenous and intranasal doses of DDAVP in diabetes insipidus. Pharmacology 1977; 15, 40-45.
- 23.
Robinson AG. DDAVP in the treatment of central diabetes insipidus. N Engl J Med
1976; 294, 507-511.
- 24. Sawyer WH, Acosta M, Balaspiri L, Judd J, Manning M. Structural changes in the arginine vasopressin molecule that enhance antidiuretic activity and specificity. Endocrinology 1974; 94 (4): 1106.
- 25. Sawyer WH, Acosta M, Manning M. Structural changes in the arginine vasopressin molecule that prolong its antidiuretic action. Endocrinology 1974;(1): 140.
- 26. Seif SM, Zenser TV, Ciarochi FF, Davis BB, Robinson AG. DDAVP treatment of central diabetes insipidus-mechanism of prolonged antidiuresis. J Clin Endocrinol Metab 1978; 46: 381-388.
- 27. Tucker ML. DDAVP- Teratogenicity in the rabbit.Data on file at Ferring Inc., 1972.
- 28.
Vavra L, Machova A, Cort JH. Official translation of the pharmacological and
Toxicological Report on DDAVP for the Ministry of Health. Prague, Czechoslovakia, 1968.
- 29. Vilhardt H, Bie P. Antidiuretic effect of perorally administered DDAVP in hydrated humans. Acta Endocrin. 1984; 105: 474.
- 30. Vilhardt H, Lundin S. Biological effect and plasma concentrations of DDAVP after intranasal and peroral administration to humans. Gen Pharmac 1986; 17: 481-483.
- 31.
Westgren V, Wittstrom C, Harris AS. Oral desmopressin in central diabetes insipidus.
Arch Disease in Childhood 1986; 61: 247.
- 32. Williams TDM, Dunger DB, Lyon CC, Lewis RJ, Taylor F, Lightman SL. Antidiuretic effect and pharmacokinetics of oral 1-Desamino-8-D-arginine vasopressin. 1. Studies in adults and children. J Clin End Metab 1986; 63: 129.
REFERENCES FOR NOCTURNAL ENURESIS
- 33.
Wille S. A Study of Desmopressin Tablets in the Treatment of Primary Nocturnal
Enuresis in Childhood - A Dose Ranging Study. Arch.Dis. Child. 1987, 62:674-677.
- 34. Läckgren G, Lilja B, Neveus T, Stenberg A. Desmopressin in the treatment of severe nocturnal enuresis in adolescents- a 7 -year follow-up study. British Journal of Urology (1998), 81.Suppl.3,17-23.
- 35. Fjellestad A, Wille S, Harris AS. Comparison of intranasal and oral desmopressin for nocturnal enuresis. Arch.Dis.Child. 1987;62:674-677.
- 36. Nørgaard JP, Rittig S, Matthiesen T. A Dose Titration and an Open Six-Week Efficacy and Safety Study of Desmopressin Tablets in the Management of Nocturnal Enuresis. J Urol.1994 Feb; 151(2):460-3
- 37. Skoog SJ. Oral Desmopressin Acetate (DDAVP) in the treatment of primary nocturnal enuresis (PNE) Today’s Therapeutic Trends Vol 16: 275-285.
- 38.
Turner KL, Stokes A. A randomized, double blind, placebo controlled, parallel study of
Desmopressin Tablets in patients with primary nocturnal enuresis. Comprehensive Medical Report. 22 January 1997 RG-84063-607.
- 39. Skoog SJ, Stokes A, Turner KL. Oral desmopressin: a randomised, double blind, placebo controlled study of effectiveness in children with primary nocturnal enuresis. J Urol 1997; 158: 1035-40.
- 40.
Wolfish NM, Barkin J, Gorodzinsky F, Schwartz R. The Canadian Enuresis Study and
Evaluation. Short and long term safety and efficacy of an oral desmopressin preparation. Scan J Urol Nephrol 36: 00-00, 2002.
- 41.
Wolfish NM, Barkin J, Gorodzinsky F, Schwartz R. The Canadian Enuresis Study and
Evaluation. Short and long term safety and efficacy of an oral desmopressin preparation. Scan J Urol Nephrol 37:22-27, 2003.