


Product Monograph - Dorzolamide Hydrochloride and Timolol Maleate Ophthalmic Solution
RECENT MAJOR LABEL CHANGES
Not applicable.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
TABLE OF CONTENTS .......................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION............................................................... 4
1 INDICATIONS.............................................................................................................. 4
1.1 Pediatrics ........................................................................................................... 4
1.2 Geriatrics............................................................................................................ 4
2 CONTRAINDICATIONS ............................................................................................... 4
4 DOSAGE AND ADMINISTRATION .............................................................................. 5
4.1 Dosing Considerations ........................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment .................................................... 5
4.4 Administration..................................................................................................... 5
4.5 Missed Dose....................................................................................................... 5
5 OVERDOSAGE ........................................................................................................... 5
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ........................ 6
7 WARNINGS AND PRECAUTIONS .............................................................................. 7
7.1 Special Populations.............................................................................................. 10
7.1.2 Breast-feeding............................................................................................. 11
7.1.3 Pediatrics .................................................................................................... 11
7.1.4 Geriatrics .................................................................................................... 11
8 ADVERSE REACTIONS ............................................................................................ 11
8.1 Adverse Reaction Overview .............................................................................. 11
8.2 Clinical Trial Adverse Reactions ........................................................................ 12
8.5 Post-Market Adverse Reactions ........................................................................ 12
9 DRUG INTERACTIONS ............................................................................................. 13
9.2 Drug Interactions Overview ............................................................................... 13
9.4 Drug-Drug Interactions...................................................................................... 13
9.5 Drug-Food Interactions ..................................................................................... 14
9.6 Drug-Herb Interactions...................................................................................... 14
9.7 Drug-Laboratory Test Interactions ..................................................................... 14
10 CLINICAL PHARMACOLOGY ................................................................................... 14
10.1 Mechanism of Action ................................................................................... 14
10.3 Pharmacokinetics........................................................................................ 15
11 STORAGE, STABILITY AND DISPOSAL .................................................................. 17
12 SPECIAL HANDLING INSTRUCTIONS ..................................................................... 17
PART II: SCIENTIFIC INFORMATION .................................................................................. 18
13 PHARMACEUTICAL INFORMATION ........................................................................ 18
14 CLINICAL TRIALS .................................................................................................... 20
14.1 Clinical Trials by Indication .......................................................................... 20
15 MICROBIOLOGY....................................................................................................... 24
16 NON-CLINICAL TOXICOLOGY ................................................................................. 24
17 SUPPORTING PRODUCT MONOGRAPHS ............................................................... 28
PATIENT MEDICATION INFORMATION .............................................................................. 29
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION (dorzolamide hydrochloride and timolol maleate) is indicated in the treatment of elevated intraocular pressure (IOP) in patients with:
- ocular hypertension
- open-angle glaucoma
when concomitant therapy is appropriate.
1.1 Pediatrics
Pediatrics (<18 years of age): Safety and effectiveness in children have not been established. No data are available to Health Canada; therefore, an indication for pediatric use has not been authorized.
1.2 Geriatrics
Geriatrics (> 65 years of age): No overall differences in effectiveness or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out (see 7.1.4 Geriatrics).
2 CONTRAINDICATIONS
Dorzolamide hydrochloride and timolol maleate is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with reactive airway disease, bronchospasm, including bronchial asthma or a history of bronchial asthma, or chronic obstructive pulmonary disease.
- Patients with sinus bradycardia, sino-atrial block, second- or third-degree atrioventricular block, overt cardiac failure, cardiogenic shock.
- Patients with severe renal impairment (CrCl < 0.5 mL/s), as dorzolamide hydrochloride and its metabolite are excreted predominantly by the kidney. Dorzolamide hydrochloride and timolol maleate has not been studied in these patients and is not recommended.
- Patients taking an oral carbonic anhydrase inhibitor, as there is potential for an additive effect with the known systemic effects of carbonic anhydrase inhibition. The concomitant administration of dorzolamide hydrochloride and timolol maleate and oral carbonic anhydrase inhibitors has not been studied and is not recommended.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- When substituting DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION for another ophthalmic antiglaucoma agent(s), discontinue the other agent(s) after proper dosing on one day, and start DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION on the following day.
- If another topical ophthalmic agent is being used, DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION and the other agent should be administered at least ten minutes apart.
4.2 Recommended Dose and Dosage Adjustment
- Adults (>18 years of age): The dose is one drop of DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION in the affected eye(s) two times daily.
- Pediatrics (<18 years of age): Health Canada has not authorized an indication for pediatric use (see 1.1 Pediatrics).
4.4 Administration
Do not allow the pipette to touch the eye or areas around the eye.
When using nasolacrimal occlusion or closing the eyelids for 2 minutes, the systemic absorption is reduced. This may result in an increase in local activity.
If the patient has difficulty administering their DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION eye drops, the assistance of a family member or caregiver may be needed.
4.5 Missed Dose
If a dose is missed, it should be applied as soon as possible. However, if it is almost time for the next dose, the missed dose should be skipped and the next dose should be taken as usual.
5 OVERDOSAGE
No data are available with regard to human overdosage by accidental or deliberate ingestion of dorzolamide hydrochloride and timolol maleate.
There have been reports of inadvertent overdosage with timolol maleate ophthalmic solution resulting in systemic effects similar to those seen with systemic beta-adrenergic blocking agents such as dizziness, headache, shortness of breath, bradycardia, bronchospasm, and cardiac arrest. The most common signs and symptoms to be expected with overdosage of dorzolamide are electrolyte imbalance, development of an acidotic state, and possibly central nervous system effects (see 8 ADVERSE REACTIONS).
Treatment should be symptomatic and supportive. Serum electrolyte levels (particularly potassium) and blood pH levels should be monitored. Studies have shown that timolol does not dialyze readily.
Specific therapeutic measures for the treatment of overdosage with timolol maleate are reproduced below for ease of reference.
Gastric lavage: If ingested.
Symptomatic bradycardia: Use atropine sulfate intravenously in a dosage of 0.25 to 2 mg to induce vagal blockade. If bradycardia persists, intravenous isoproterenol hydrochloride should be administered cautiously. In refractory cases, the use of a transvenous cardiac pacemaker may be considered.
Hypotension: Use sympathomimetic pressor drug therapy, such as dopamine, dobutamine or levarterenol. In refractory cases, the use of glucagon hydrochloride has been reported to be useful.
Bronchospasm: Use isoproterenol hydrochloride. Additional therapy with aminophylline may be considered.
Acute cardiac failure: Conventional therapy with digitalis, diuretics and oxygen should be instituted immediately. In refractory cases, the use of intravenous aminophylline is suggested. If necessary, this may be followed by glucagon hydrochloride which has been reported to be useful.
Heart block (second or third degree): Use isoproterenol hydrochloride or a transvenous cardiac pacemaker.
| For management of a suspected drug overdose, contact your regional poison control centre. |
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTALMIC SOLUTION is supplied as a sterile isotonic, buffered, slightly viscous, aqueous solution. Each milliliter of DORZOLAMIDE HYDROCHLORIDE and TIMOLOL MALEATE OPHTHALMIC SOLUTION contains 20 mg dorzolamide (22.3 mg of dorzolamide hydrochloride) and 5 mg timolol (6.83 mg of timolol maleate) as the active ingredients.
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE is a clear, colourless to nearly colourless, slightly viscous solution supplied in a low-density polyethylene, white, Boston round bottle topped with a linear low-density polyethylene, white, controlled dropper tip, and covered
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Ophthalmic | Solution, each mL contains dorzolamide 20 mg and timolol 5 mg | Hydroxyethyl cellulose, mannitol, sodium citrate dihydrate, sodium hydroxide, water for injection Benzalkonium chloride (0.0075%) is added as a preservative. |
with a polypropylene, blue, extended tip, short skirt, lineless cap. Tamper evidence is provided by a safety strip on the container label.
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC Solution, is available as a 10 mL fill in a 10 mL bottle.
7 WARNINGS AND PRECAUTIONS
General
As with other topically-applied ophthalmic agents, the active substances may be absorbed systemically. Dorzolamide is a sulfonamide and timolol is a beta-blocker. Therefore, the same types of adverse reactions found with systemic administration of sulfonamides or beta-blockers may occur with topical administration, including severe reactions such as Stevens-Johnson syndrome and toxic epidermal necrolysis.
If signs of serious reactions or hypersensitivity occur, discontinue use of this preparation.
The management of patients with acute angle-closure glaucoma requires therapeutic interventions in addition to ocular hypotensive agents. Dorzolamide hydrochloride and timolol maleate has not been studied in patients with acute angle-closure glaucoma.
Carcinogenesis and Mutagenesis
Carcinogenicity
Dorzolamide Hydrochloride
The results of studies of dorzolamide hydrochloride administrated orally to male and female Sprague-Dawley rats have shown that urinary bladder papillomas were seen in male rats in the highest dosage group of 20 mg/kg/day and no treatment-related tumors were seen in female and male mice given oral doses up to 75 mg/kg/day.
Timolol Maleate
The results of studies of timolol maleate in rats have shown an increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day and increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinoma in female mice at 500 mg/kg/day.
See 16 NON-CLINICAL TOXICOLOGY.
Mutagenicity
Dorzolamide Hydrochloride
Dorzolamide hydrochloride was devoid of mutagenic potential in the conducted evaluations.
Timolol Maleate
Timolol Maleate was devoid of mutagenic potential in the conducted evaluations.
See 16 NON-CLINICAL TOXICOLOGY.
Cardiovascular
Because of the timolol maleate component, cardiac failure should be adequately controlled before beginning therapy with DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION (dorzolamide hydrochloride and timolol maleate).
Patients with a history of cardiac disease, including cardiac failure, should be watched for signs of deterioration of these diseases, and pulse rates should be checked.
Due to its negative effect on conduction time, beta blockers should be given with caution to patients with first degree heart block.
Respiratory reactions and cardiac reactions, including death due to bronchospasm in patients with asthma and rarely death in association with cardiac failure, have been reported following administration of timolol maleate ophthalmic solution.
Patients with severe peripheral circulatory disturbance/disorders (e.g., severe forms of Raynaud’s disease or Raynaud’s syndrome) should be treated with caution.
Contamination
To minimize the contamination potential, patients should not touch the eye, the area around the eye, or any other surface with the tip of the container. It may become contaminated with bacteria. This can cause eye infections. This could lead to serious damage of the eye including loss of vision. Keep the tip of the container away from contact with any surface.
Driving and Operating Machinery
Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Endocrine and Metabolism
Masking of Hypoglycemic Symptoms in Patients with Diabetes Mellitus
Beta-adrenergic blocking agents should be administered with caution in patients subject to spontaneous hypoglycemia or to diabetic patients (especially those with labile diabetes) who are receiving insulin or oral hypoglycemic agents. Beta-adrenergic blocking agents may mask the signs and symptoms of acute hypoglycemia.
Masking of Thyrotoxicosis
Beta-adrenergic blocking agents may mask certain clinical signs of hyperthyroidism (e.g., tachycardia). Patients suspected of developing thyrotoxicosis should be managed carefully to avoid abrupt withdrawal of beta-adrenergic blocking agents which might precipitate a thyroid storm.
Hepatic/Biliary/Pancreatic
Dorzolamide hydrochloride and timolol maleate has not been studied in patients with hepatic impairment and therefore should be used with caution in such patients.
Immune
Immunology and Hypersensitivity
In clinical studies, local ocular adverse effects, primarily conjunctivitis and eyelid reactions, were reported with chronic administration of dorzolamide hydrochloride ophthalmic solution. Some of these reactions had the clinical appearance and course of an allergic-type reaction that resolved upon discontinuation of drug therapy. Similar reactions have been reported with dorzolamide hydrochloride and timolol maleate. If such reactions are observed, discontinuation of treatment with DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should be considered.
While taking beta-blockers, patients with a history of atopy or a history of severe anaphylactic reaction to a variety of allergens may be more reactive to accidental, diagnostic, or therapeutic repeated challenge with such allergens. Such patients may be unresponsive to the usual doses of epinephrine used to treat anaphylactic reactions.
Monitoring and Laboratory Tests
Dorzolamide hydrochloride and timolol maleate was not associated with clinically meaningful electrolyte disturbances.
Neurologic
Muscle Weakness
Beta-adrenergic blockade has been reported to increase muscle weakness consistent with certain myasthenic symptoms (e.g., diplopia, ptosis and generalized weakness). Timolol has been reported rarely to increase muscle weakness in some patients with myasthenic symptoms.
Cerebrovascular Insufficiency
Because of potential effects of beta-adrenergic blocking agents relative to blood pressure and pulse, these agents should be used with caution in patients with cerebrovascular insufficiency. If signs or symptoms suggesting reduced cerebral blood flow develop following initiation of therapy with DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION, alternative therapy should be considered.
Ophthalmologic
Corneal Edema
There is an increased risk of developing irreversible corneal edema in a subset of glaucoma patients with endothelial abnormalities including cellular density and/or morphology. In this group of patients evaluation of the cornea, with particular attention to the corneal endothelium, is recommended prior to and during treatment with DORZOLAMIDE HYDROCHLORIDE AND
TIMOLOL MALEATE OPHTHALMIC SOLUTION.
Corneal Edema and Irreversible Corneal Decompensation
Corneal edema and irreversible corneal decompensation has been reported in patients with pre-existing chronic corneal defects and/or a history of intraocular surgery while using dorzolamide. DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should be used with caution in such patients.
Contact Lenses
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION contains the preservative benzalkonium chloride, which may be deposited in soft contact lenses; therefore, DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should not be administered while wearing these lenses. The lenses should be removed before application of the drops and not be reinserted earlier than 15 minutes after use.
Choroidal Detachment
Choroidal detachment has been reported with administration of aqueous suppressant therapy (e.g., timolol, acetazolamide) after filtration procedures. Management of eyes with chronic or recurrent choroidal detachment should include stopping all forms of aqueous suppressant therapy and treating endogenous inflammation vigorously.
Peri-Operative Considerations
Surgical Anesthesia
The necessity or desirability of withdrawal of beta-adrenergic blocking agents prior to major surgery is controversial. If necessary during surgery, the effects of beta-adrenergic blocking agents may be reversed by sufficient doses of such agonists as isoproterenol, dopamine, dobutamine or levarterenol (see 5 OVERDOSAGE).
Respiratory
In patients with mild/moderate chronic obstructive pulmonary disease (COPD), DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should be used with caution, and only if the potential benefit outweighs the potential risk.
7.1 Special Populations
- 7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
7.1.2 Breast-feeding
It is not known whether dorzolamide hydrochloride is excreted in human milk. Timolol maleate does appear in human milk. Because of the potential for serious adverse reactions on the nursing infant, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
In a study of dorzolamide hydrochloride in lactating rats, decreases in body weight gain of 5 to
7% in offspring at an oral dose of 7.5 mg/kg/day (94 times the maximum recommended human ophthalmic dose) were seen during lactation. A slight delay in postnatal development (incisor eruption, vaginal canalization and eye openings), secondary to lower fetal body weight, was noted at 7.5 mg/kg/day (94 times the maximum recommended human ophthalmic dose).
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (>65 years of age): Of the total number of patients in clinical studies of dorzolamide hydrochloride and timolol maleate, 49% were 65 years of age and over, while 13% were 75 years of age and over.
No overall differences in effectiveness or safety were observed between these patients and younger adult patients, but greater sensitivity of some older individuals cannot be ruled out.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Adverse reactions have been seen with dorzolamide hydrochloride and timolol maleate, thus potential adverse reactions following the use of DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION may include:
Dorzolamide Hydrochloride
Headache; eyelid inflammation; eyelid crusting; eyelid irritation; asthenia/fatigue; iridocyclitis; rash; dizziness; paraesthesia; superficial punctate keratitis, transient myopia (which resolved upon discontinuation of therapy); signs and symptoms of local reactions including palpebral reactions and systemic allergic reactions including angioedema, bronchospasm, urticaria, epistaxis and pruritus; throat irritation, dry mouth.
Timolol Maleate (topical formulation)
Signs and symptoms of ocular irritation, including conjunctivitis, blepharitis, keratitis, and decreased corneal sensitivity, dry eyes; visual disturbances, including refractive changes (due to withdrawal of miotic therapy in some cases), diplopia, and ptosis; choroidal detachment following filtration surgery, tinnitus; aggravation or precipitation of certain cardiovascular pulmonary and other disorders presumably related to effects of systemic beta-blockade has been reported (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS). These include bradycardia; arrhythmia; hypotension; syncope; heart block; cerebrovascular accident; cerebral ischemia; palpitation; cardiac arrest, edema, claudication, Raynaud’s phenomenon, cold hands and feet; congestive heart failure, and in insulin-dependent diabetics, masked symptoms of hypoglycemia have been reported rarely. In clinical trials, slight reduction of the resting heart rate in some patients; bronchospasm (predominantly in patients with pre-existing bronchospastic disease); cough; headache; asthenia; fatigue; chest pain; alopecia; psoriasiform rash or exacerbation of psoriasis; signs and symptoms of allergic reactions including anaphylaxis angioedema, urticaria, localized and generalized rash; dizziness; increase in signs and symptoms of myasthenia gravis; insomnia; nightmares; memory loss; paresthesia; diarrhea, dyspepsia, dry mouth; abdominal pain; decreased libido, Peyronie’s disease; sexual dysfunction; systemic lupus erythematous; myalgia.
Timolol Maleate (systemic formulation)
Adverse reactions reported in clinical experience with oral timolol maleate may be considered potential side effects of ophthalmic timolol maleate.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
In clinical studies, no adverse reactions specific to this combination drug have been observed. Adverse reactions have been limited to those that were reported previously with dorzolamide hydrochloride and/or timolol maleate. In general, common adverse reactions were mild and did not cause discontinuation.
During clinical studies of up to 15 months duration, 1035 patients were treated with dorzolamide hydrochloride and timolol maleate. Approximately 2.4% of all patients discontinued therapy with dorzolamide hydrochloride and timolol maleate because of local ocular adverse reactions. Approximately 1.2% of all patients discontinued use because of local adverse reactions suggestive of allergy or hypersensitivity.
The most frequently reported drug-related adverse reactions were: ocular burning and stinging (10.7%), taste perversion (5.8%), corneal erosion (2.0%), conjunctival injection (1.8%), blurred vision (1.4%), tearing (1.0%), and ocular itching. Urolithiasis was reported rarely (0.9%).
8.5 Post-Market Adverse Reactions
The following adverse reactions have been reported in post-marketing experience: dyspnea, respiratory failure, contact dermatitis, bradycardia, heart block, choroidal detachment following filtration surgery, nausea, corneal edema in glaucoma patients with endothelial abnormalities including cellular density and/or morphology, Stevens-Johnson syndrome, and toxic epidermal necrolysis.
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Specific drug interaction studies have not been performed with dorzolamide hydrochloride and timolol maleate.
In clinical studies, dorzolamide hydrochloride and timolol maleate was used concomitantly with the following systemic medications without evidence of adverse interactions: ACE-inhibitors, calcium channel blockers, diuretics, non-steroidal anti-inflammatory drugs including acetylsalicylic acid, and hormones (e.g., estrogen, insulin, thyroxine). However, the potential for interactions with any drug should be considered.
9.4 Drug-Drug Interactions
The drugs listed below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
The following drug interactions have been associated either with the components of DORZOLAMIDE HYDROCHLORIDE and TIMOLOL MALEATE OPHTHALMIC SOLUTION or with other beta-blockers or sulfonamides.
Acid-base Disturbances
The dorzolamide component of DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION is a carbonic anhydrase inhibitor and, although administered topically, it is absorbed systemically. In clinical studies, dorzolamide hydrochloride ophthalmic solution was not associated with acid-base disturbances. However, these disturbances have been reported with oral carbonic anhydrase inhibitors and have, in some instances, resulted in drug interactions (e.g., toxicity associated with high-dose salicylate therapy). Therefore, the potential for such drug interactions should be considered in patients receiving DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION.
Calcium Channel Blockers or Catecholamine-depleting Drugs
The potential exists for additive effects and production of hypotension, atrioventricular conduction disturbances, left ventricular failure and/or marked bradycardia when timolol maleate ophthalmic solution is administered together with oral calcium channel blockers, catecholamine-depleting drugs antiarrhythmics, parasympathomimetics, or beta-adrenergic blocking agents.
Quinidine
Potentiated systemic beta-blockade (e.g., decreased heart rate, depression) has been reported during combined treatment with CYP2D6 inhibitors (e.g., quinidine, SSRIs) and timolol.
Clonidine
Oral beta-adrenergic blocking agents may exacerbate the rebound hypertension which can follow the withdrawal of clonidine. If the two drugs are co-administered, the beta-adrenergic blocking agent should be withdrawn several days before the gradual withdrawal of clonidine. If replacing clonidine by beta-blocker therapy, the introduction of beta-adrenergic blocking agents should be delayed for several days after clonidine administration has stopped.
Beta-adrenergic Blockers
Patients who are already receiving a beta-adrenergic blocking agent systemically and who are given DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION should be observed for a potential additive effect either on the IOP or on the known systemic effects of beta-blockade. The concomitant use of two topical beta-adrenergic blocking agents is not recommended.
Epinephrine
Although DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION used alone has little or no effect on pupil size, mydriasis resulting from concomitant use of timolol maleate and epinephrine has been reported occasionally.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Clinically important changes in standard laboratory parameters were rarely associated with the administration of systemic timolol maleate. Slight increases in blood urea nitrogen, serum potassium, serum uric acid and triglycerides, and slight decreases in hemoglobin, hematocrit and HDL-cholesterol occurred, but were not progressive or associated with clinical manifestations.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION is a combination of dorzolamide hydrochloride and timolol maleate. Each of these two components decreases elevated IOP by reducing aqueous humor secretion but does so by a different mechanism of action.
Dorzolamide hydrochloride is a potent inhibitor of human carbonic anhydrase II (CA-II). Inhibition of carbonic anhydrase in the ciliary processes of the eye decreases aqueous humor secretion, presumably by slowing the formation of bicarbonate ions with subsequent reduction in sodium and fluid transport. Timolol maleate is a nonselective beta-adrenergic receptor blocking agent that does not have significant intrinsic sympathomimetic, direct myocardial depressant, or local anesthetic (membrane-stabilizing) activity. The combined effect of these two agents results in additional IOP reduction compared to either component administered alone.
Following topical administration, dorzolamide hydrochloride and timolol maleate reduce elevated IOP, whether or not associated with glaucoma. Elevated IOP is a major risk factor in the pathogenesis of optic nerve damage and glaucomatous visual field loss. The higher the level of IOP, the greater the likelihood of glaucomatous visual field loss and optic nerve damage. Dorzolamide hydrochloride and timolol maleate reduces IOP without the common side effects of miotics such as night blindness, accommodative spasm and pupillary constriction.
10.3 Pharmacokinetics
Dorzolamide Hydrochloride
Absorption
Unlike oral carbonic anhydrase inhibitors, topically-applied dorzolamide hydrochloride exerts its effects at substantially low doses and therefore with less systemic exposure. When applied topically, dorzolamide reaches the systemic circulation.
Distribution
To assess the potential for systemic carbonic anhydrase inhibition following topical administration, drug and metabolite concentrations in red blood cells (RBCs) and plasma, and carbonic anhydrase inhibition in RBCs were measured. Dorzolamide accumulates in RBCs during chronic dosing as a result of selective binding to CA-II while extremely low concentrations of free drug in plasma are maintained.
Metabolism
The parent drug forms a single N-desethyl metabolite that inhibits CA-II less potently than the parent drug but also inhibits a less active isoenzyme (carbonic anhydrase I (CA-I)). The metabolite also accumulates in RBCs where it binds primarily to CA-I. Dorzolamide binds moderately to plasma proteins (approximately 33%).
Elimination
Dorzolamide is excreted unchanged in the urine; the metabolite is also excreted in urine. After dosing ends, dorzolamide washes out of RBCs in a non-linear manner, resulting in a rapid decline of drug concentration initially, followed by a slower elimination phase with a half-life of about four months.
To simulate the maximum systemic exposure after long term topical ocular administration, dorzolamide was given orally to eight healthy subjects for up to 20 weeks. The oral dose of 4 mg/day closely approximates the maximum amount of dorzolamide delivered by topical ocular administration of dorzolamide hydrochloride 2% t.i.d. (ter in die (three times a day)) Dorzolamide and metabolite reached steady state by 4 and 13 weeks, respectively, and the following observations were noted:
- In plasma, concentrations of dorzolamide and metabolite were generally below the assay limit of quantitation (15 nM) indicating almost no free drug or metabolite;
- In RBCs, dorzolamide concentrations approached the binding capacity of CA-II (20–25 mcM) and metabolite concentrations approached 12–15 mcM, well below the binding capacity of CA-I (125–155 mcM);
- In RBCs, inhibition of CA-II activity and total carbonic anhydrase activity was below the degree of inhibition anticipated to be necessary for a pharmacological effect on renal function and respiration.
Timolol Maleate
Absorption
In a study of plasma drug concentration in six subjects, the systemic exposure to timolol was determined following twice daily topical administration of timolol maleate ophthalmic solution 0.5%. The mean peak plasma concentration following morning dosing was 0.46 ng/mL and following afternoon dosing was 0.35 ng/mL.
By comparison to plasma concentration (10 to 20 ng/mL) following oral 5 mg dose, it was estimated that timolol was approximately 50% bioavailable systemically following intraocular administration.
Distribution
Timolol maleate combines reversibly with a part of the cell membrane, the beta-adrenergic receptor, and thus inhibits the usual biologic response that would occur with stimulation of that receptor. This specific competitive antagonism blocks stimulation of the beta-adrenergic receptors by catecholamines having beta-adrenergic stimulating (agonist) activity, whether these originate from an endogenous or exogenous source. Reversal of this blockade can be accomplished by increasing the concentration of the agonist, which will restore the usual biologic response.
Metabolism
Timolol maleate (S(-) enantiomer) is significantly metabolized after oral and ophthalmic administration. Based on correlation with debrisoquine metabolism, timolol metabolism is mediated primarily by cytochrome P-450 2D6. Dorzolamide is eliminated primarily by urinary excretion as unchanged drug. The metabolic pathway utilized by dorzolamide (cytochrome P-450 2C9, 2C19, and 3A4) is different from that utilized by timolol. In vitro studies using human liver microsomes have shown that dorzolamide at concentrations up to 200 mcM does not affect the metabolism of timolol. Therefore, there is little potential for altered systemic exposure to either drug when administered in combination. Timolol is moderately (< 60%) bound to plasma proteins.
Elimination
The drug and the metabolites (hydroxyethylamino, hydroxyethylglycolamino derivatives and a third minor metabolite that results from the hydroxylation of a terminal methyl group on the tertiary butylamino moiety) are excreted primarily via the kidney.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15 – 25 °C (59° - 77°F). Protect from light.
After first opening store at 15° - 25°C (59° - 77°F) for up to 62 days.
Keep out of sight and reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
Keep the tip of the container away from the eye, area around the eye, or contact with any surface.
See 4.1 Dosing Considerations, 4.4 Administration, 7 WARNINGS AND PRECAUTIONS, Contamination and 7 WARNINGS AND PRECAUTIONS, Contact Lenses.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION contains dorzolamide hydrochloride and timolol maleate
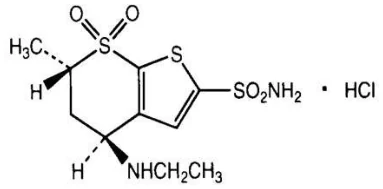
Dorzolamide Hydrochloride
Proper name: dorzolamide hydrochloride
Chemical name: (4S-trans)-4-(Ethylamino)-5,6-dihydro-6-methyl- 4H thieno[2,3- b]thiopyran-2-sulfonamide7,7-dioxide monohydrochloride. Dorzolamide hydrochloride is optically active
Molecular formula and molecular mass: C10H16N2O4S3.HCl, 360.91 g/mol
Structural formula:
Physicochemical properties:
Description: Dorzolamide hydrochloride is a white to off-white, free flowing crystalline powder.
Solubility: Soluble in water and slightly soluble in methanol.
Melting point: about 264 °C.
The specific rotation: α25° (C = 1, water) = ~ -17°.
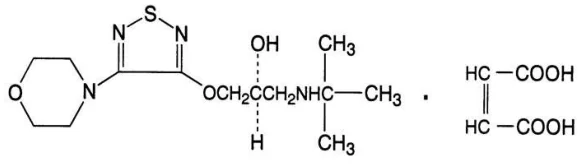
Timolol Maleate
Proper name: timolol maleate
Chemical name: (S)-1-[(1,1-dimethylethyl)amino]-3-[[4-(4- morpholinyl)-1,2,5-thiadiazol-3-yl]oxy]-2- propanol(Z)-2-butenedioate(1:1) (salt)active.
Molecular formula and molecular mass: C13H24N4O3S.C4H4O4, 432.50 g/mol
Structural formula:
Physicochemical properties:
Description: Timolol maleate is a beta-adrenergic receptor blocking agent. It possesses an asymmetric carbon atom in its structure and is provided as the levo isomer. It is a white odourless, crystalline powder.
Solubility: soluble in water, methanol and alcohol.
Melting point: 201.5 °C to 202.5 °C.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Elevated Intraocular Pressure
Table 2 – Summary of patient demographics for clinical trials in the treatment of elevated intraocular pressure (IOP)
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) | Mean age (Range) | Sex |
| Study 1 | 3-month, parallel, randomized, double-masked, active-controlled, multicenter study | 2.0% dorzolamide/0.5% timolol solution (dorzolamide hydrochloride and timolol maleate) ophthalmic bid, 3 months 2% dorzolamide solution and 0.5% timolol solution (concomitant group) ophthalmic bid, 3 months | 299 | 63.1 years old (23–84) | M: 113 F: 186 |
| Study 2 | 3-month, parallel, randomized, double-masked, active-controlled, multicenter clinical trial | 2.0% dorzolamide/0.5% timolol solution (dorzolamide hydrochloride and timolol maleate) ophthalmic bid, 3 months 2% dorzolamide solution ophthalmic tid, 3 months 0.5% timolol solution ophthalmic bid, 3 months | 335 | 62.0 years old (27-84) | M: 171 F: 164 |
| Study 3 | 3-month, parallel, randomized, double-masked, active-controlled multicenter study | 2.0% dorzolamide/0.5% timolol solution (dorzolamide hydrochloride and timolol maleate) | 253 | 63.7 years old (28-88) | M: 111 F: 142 |
Clinical studies (Studies 1 - 4) of up to 15 months duration were conducted to compare the IOP-lowering effect of dorzolamide hydrochloride and timolol bid (dosed morning and bedtime) to individually and concomitantly administered 0.5% timolol and 2.0% dorzolamide in patients with glaucoma or ocular hypertension for whom concomitant therapy is appropriate. This includes both untreated patients and patients inadequately controlled with timolol monotherapy. The IOP-lowering effect of dorzolamide hydrochloride and timolol bid was greater than that of monotherapy with either 2% dorzolamide tid or 0.5% timolol bid. The IOP-lowering effect of dorzolamide hydrochloride and timolol bid was equivalent to that of concomitant therapy with dorzolamide bid and timolol bid.
Comparison to Concomitant Therapy (Patients initiated on timolol therapy)
In a 3-month randomized, double-masked, parallel clinical study, patients receiving dorzolamide hydrochloride and timolol bid (n = 151) were compared to patients receiving 0.5% timolol bid plus 2.0% dorzolamide bid concomitantly (n = 148). At morning trough (hour 0) and morning peak (hour 2), patients receiving dorzolamide hydrochloride and timolol experienced IOP-lowering that was equivalent to that seen in the patients receiving the individual components concomitantly. Reductions in IOP were observed relative to the baseline value obtained after 2 weeks of 0.5% timolol bid monotherapy (Study 1, Table 3).
ophthalmic bid, 3 months 2% dorzolamide solution ophthalmic tid, 3 months 0.5% timolol solution ophthalmic bid, 3 months | |||||
| Study 4 | 3-month, multicenter, parallel, randomized, double-masked clinical trial with 9-month open label extension | 2.0% dorzolamide/0.5% timolol solution (dorzolamide hydrochloride and timolol maleate) ophthalmic bid 2% dorzolamide solution and 0.5% timolol solution (concomitant group) ophthalmic bid | 242 | 61.2 years old (22 to 84) | M: 121 F: 121 |
Table 3 - Results of study 1 in the treatment of elevated intraocular pressure (IOP)
Comparison to Monotherapy (Patients washed out from previous therapy)
A 3-month randomized, double-masked parallel clinical study compared dorzolamide hydrochloride and timolol maleate bid (n = 114) to 0.5% timolol bid monotherapy (n = 112) and 2.0% dorzolamide tid monotherapy (n = 109) in patients for whom concomitant therapy was appropriate. After a 3-week washout of all previous ocular hypotensive therapies, those patients receiving dorzolamide hydrochloride and timolol maleate experienced IOP-lowering at both morning trough (hour 0) and morning peak (hour 2) that was greater than that seen in patients receiving either component alone (Study 2, Table 4).
Table 4 - Results of study 2 in the treatment of elevated intraocular pressure (IOP)
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for active controla |
| Additional mean reduction in IOP from timolol baseline (mmHg)b [mean % reduction in IOP] | Day 90 (hour 0): 4.2 [16.3%] Day 90 (hour 2): 5.4 [21.6%) | Day 90 (hour 0): 4.2 [16.3%], p>0.05 vs. dorzolamide hydrochloride and timolol maleate Day 90 (hour 2): 5.4 [21.8%], p>0.05 vs. dorzolamide hydrochloride and timolol maleate |
a. Active control: 0.5% timolol bid + 2.0% dorzolamide bid b. Patients were required to have baseline IOP ≥ 22 mmHg for enrollment. | ||
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for active controla |
| Additional mean reduction in IOP from baseline (mmHg)b [mean % reduction in IOP] | Day 90 (hour 0): 7.7 [27.4%] Day 90 (hour 2): 9.0 [32.7%] | 2.0% dorzolamide tid : Day 90 (hour 0): 4.6 [15.5%], p<0.001 vs. dorzolamide hydrochloride and timolol maleate Day 90 (hour 2): 5.4 [19.8%], p<0.001 vs. dorzolamide hydrochloride and timolol maleate 0.5% timolol bid : Day 90 (hour 0): 6.4 [22.2%], p=0.003 vs. dorzolamide hydrochloride and timolol maleate Day 90 (hour 2): 6.3 [22.6%], p<0.001 vs. dorzolamide hydrochloride and timolol maleate |
a. Active controls: 0.5% timolol bid or 2.0% dorzolamide tid b. Patients were required to have baseline IOP ≥ 24 mmHg for enrollment. | ||
Comparison to Monotherapy (Patients initiated on timolol therapy)
In a 3-month randomized, double-masked parallel clinical study in patients with elevated IOP inadequately controlled after 3 weeks of 0.5% timolol bid monotherapy, patients receiving dorzolamide hydrochloride and timolol maleate bid (n = 104) experienced IOP-lowering at both morning trough (hour 0) and morning peak (hour 2) that was greater than that seen in patients receiving either 0.5% timolol bid monotherapy (n = 98) or 2.0% dorzolamide tid monotherapy (n = 51) (Study 3, Table 5).
Table 5 - Results of study 3 in the treatment of elevated intraocular pressure (IOP)
Long-term Studies
Open-label extensions of two studies were conducted for up to 12 months. During this period, the IOP-lowering effect of dorzolamide hydrochloride and timolol maleate bid was demonstrated throughout the day and this effect was maintained during long-term administration (Study 4, Table 6).
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for active controla |
| Additional mean reduction in IOP from timolol baseline (mmHg)b [mean % reduction in IOP] | Day 90 (hour 0): 2.8 [10.6%] Day 90 (hour 2): 4.4 [17.3%] | 2.0% dorzolamide tid : Day 90 (hour 0): 1.4 [4.9%], Treatment Difference: -5.63 95% CI: (-10.15 to -1.12) Day 90 (hour 2): 2.0 [7.4%], Treatment Difference: -9.71 95% CI: (-14.78 to -4.64) 0.5% timolol bid : Day 90 (hour 0): 1.7 [6.7%], Treatment Difference: -3.91 95% CI: (-7.63 to -0.19) Day 90 (hour 2): 1.6 [6.6%], Treatment Difference: -11.13 95% CI: (-15.35 to -6.90) |
a. Active controls: 0.5% timolol bid or 2.0% dorzolamide tid b. Patients were required to have baseline IOP ≥ 22 mmHg for enrollment. | ||
Table 6 - Results of study 4 in the treatment of elevated intraocular pressure (IOP
15 MICROBIOLOGY
DORZOLAMIDE HYDROCHLORIDE AND TIMOLOL MALEATE OPHTHALMIC SOLUTION contains the preservative benzalkonium chloride as an antimicrobial preservative.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Toxicity
The oral LD50 of dorzolamide hydrochloride is 1320 mg/kg (3960 mg/m2) in male and female mice and 1927 mg/kg (11,369 mg/m2) in female rats.
The oral LD50 of timolol maleate is 1190 mg/kg (3570 mg/m2) in female mice and 900 mg/kg (5310 mg/m2) in female rats.
Chronic Toxicology
Dorzolamide Hydrochloride and Timolol Maleate
No adverse ocular effects were seen in rabbits and dogs treated topically with dorzolamide hydrochloride and timolol maleate ophthalmic solution in studies lasting 3 and 6 months, respectively.
No adverse ocular effects were seen in monkeys and rabbits treated topically with 2% dorzolamide hydrochloride and 0.5% timolol maleate ophthalmic solutions administered concomitantly in studies lasting 15 days and 1 month, respectively.
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for active controla |
| Additional mean reduction in IOP from timolol baseline (mmHg)b [mean % reduction in IOP] | Day 90 (hour 0): 3.6 [13.8%] Day 90 (hour 2): 5.0 [19.7%] Day 90 (hour 8): 3.7 [14.9%] Month 12 (hour 0): 3.5 [13.7%] Month 12 (hour 2): 5.1 [20.5%] | Day 90 (hour 0): 4.1 [15.5%], p=0.990 vs. dorzolamide hydrochloride and timolol maleate Day 90 (hour 2): 4.9 [19.1%], p=0.997 vs. dorzolamide hydrochloride and timolol maleate Day 90 (hour 8): 4.3 [17.4%], P=0.967 vs. dorzolamide hydrochloride and timolol maleate Month 12 (hour 0): 3.2 [12.1%] Month 12 (hour 2): 5.0 [20.0%] |
a. Active control: 0.5% timolol bid and 2.0% dorzolamide tid b. Patients were required to have baseline IOP ≥ 22 mmHg for enrollment. | ||
Timolol Maleate
No adverse ocular effects were observed in rabbits and dogs administered timolol maleate ophthalmic solution topically in studies lasting 1 and 2 years, respectively.
Dorzolamide Hydrochloride
In repeated oral dose toxicity studies of dorzolamide hydrochloride in rodents, dogs and monkeys, the following effects were noted:
- An increased incidence of urothelial hyperplasia was noted in rats and mice. This is a class-effect of carbonic anhydrase inhibitors (CAIs) specific to rodents and is secondary to increased urinary sodium, potassium, pH, and crystals.
- Another class effect of CAIs seen only in rodents was renal papillary cytoplasmic granularity associated with potassium depletion in the kidney. No-effect levels for these microscopic changes were not observed. However, these findings are rodent specific and not seen in monkeys at oral doses up to 50 mg/kg/day (625 times the maximum recommended human ophthalmic dose).
- Metabolic acidosis and the related gastric mucous neck cell hyperplasia were seen in dogs and monkeys. In dogs, the gastric change was seen at a dose as low as 0.2 mg/kg/day in a one-month study, but disappeared with continued dosing and was absent at one year at a dose as high as 2 mg/kg/day. In monkeys in a one-month study, the gastric change was seen at a dose of 50 mg/kg/day orally, but no effects were seen at 10 mg/kg/day orally, or when 0.4 mg/kg/day (~5 times the maximum recommended human ophthalmic dose) was applied topically to the eye for 1 year.
- Another high dose phenomenon observed in dogs and monkeys (doses ≥ 1.5 mg/kg/day and 50 mg/kg/day, respectively) in short term studies was decreased remodeling of bone, probably as a result of inhibition of carbonic anhydrase in osteoclasts. Longer term studies in dogs showed the change was transient.
- Marginal non-progressive decreases in some erythroid parameters were seen in dogs and monkeys at dorzolamide plasma levels of 50 ng/mL in dogs and 1660 ng/mL in monkeys. The plasma levels of dorzolamide in humans given the maximum recommended ophthalmic dose are generally ≤ 5 ng/mL.
Carcinogenicity
Dorzolamide Hydrochloride
In a two-year study of dorzolamide hydrochloride administered orally to male and female Sprague-Dawley rats, urinary bladder papillomas were seen in male rats in the highest dosage group of 20 mg/kg/day (250 times the maximum recommended human ophthalmic dose). Papillomas were not seen in rats given oral doses equivalent to approximately twelve times the maximum recommended human ophthalmic dose. No treatment-related tumors were seen in a 21-month study in female and male mice given oral doses up to 75 mg/kg/day (~900 times the maximum recommended human ophthalmic dose).
The increased incidence of urinary bladder papillomas seen in the high-dose male rats is a class-effect of CAIs in rats and is secondary to increased urinary sodium, potassium, pH and crystals, all changes induced by CAIs. Rats are particularly prone to developing papillomas in response to foreign bodies, compounds causing crystalluria and sodium salts of diverse compounds that are inert when given as calcium salts.
No changes in bladder urothelium were seen in dogs given oral dorzolamide for one year at 2 mg/kg/day or in monkeys given oral dorzolamide for one month at 50 mg/kg/day (the urothelial changes in the bladder occurred with oral dosing in rats within one month). In addition, monkeys dosed topically to the eye with 0.4 mg/kg/day (~5 times the maximum recommended human ophthalmic dose) for 1 year had no urothelial changes in the bladder.
Timolol Maleate
In a 2-year oral study of timolol maleate in rats, there was a statistically significant (p ≤ 0.05) increase in the incidence of adrenal pheochromocytomas in male rats administered 300 mg/kg/day (300 times the maximum recommended human oral dose of 60 mg of timolol, as one drop of timolol maleate 0.5% ophthalmic solution contains about 0.2 mg of timolol). Similar differences were not observed in rats administered oral doses equivalent to 25 or 100 times the maximum recommended human oral dose.
In a lifetime oral study in mice, there were statistically significant (p ≤ 0.05) increases in the incidence of benign and malignant pulmonary tumors, benign uterine polyps and mammary adenocarcinoma in female mice at 500 mg/kg/day (500 times the maximum recommended human dose), but not at 5 or 50 mg/kg/day. In a subsequent study in female mice, in which post-mortem examinations were limited to uterus and lungs, a statistically significant increase in the incidence of pulmonary tumors was again observed at 500 mg/kg/day.
The increased occurrence of mammary adenocarcinoma was associated with elevations in serum prolactin which occurred in female mice administered timolol at 500 mg/kg/day, but not at doses of 5 or 50 mg/kg/day. An increased incidence of mammary adenocarcinomas in rodents has been associated with administration of several other therapeutic agents which elevate serum prolactin, but no correlation between serum prolactin levels and mammary tumors has been established in man. Furthermore, in adult human female subjects who received oral dosages of up to 60 mg of timolol maleate, the maximum recommended human oral dosage, there were no clinically meaningful changes in serum prolactin.
Genotoxicity
Dorzolamide Hydrochloride
Dorzolamide hydrochloride was devoid of mutagenic potential when evaluated in the following 5 tests: (1) in vivo (mouse) in the cytogenetic assay at doses up to 500 mg/kg/day (6250 times the maximum recommended human ophthalmic dose); (2) in vitro in the chromosomal aberration assay; (3) in the alkaline elution assay; (4) in the V-79 assay (doses up to 10 mcM); and (5) in the Ames test, in which the highest concentration of dorzolamide hydrochloride used, 10,000 mcg/plate, did not result in a two-fold or greater increase in revertants with tester strains of S. typhimurium and E. coli.
Timolol Maleate
Timolol maleate was devoid of mutagenic potential when evaluated in vivo (mouse) in the micronucleus test and cytogenetic assay (doses up to 800 mg/kg) and in vitro in a neoplastic cell transformation assay (up to 100 mcg/mL). Using the Ames test, the highest concentrations of timolol employed, 5000 or 10,000 mcg/plate, were associated with statistically significant elevations (p ≤ 0.05) of revertants observed with tester strain TA 100 (in seven replicate assays), but not in the remaining three strains. In the assays with tester strain TA 100, no consistent dose-response relationship was observed, nor did the ratio of test to control revertants reach 2. A ratio of 2 is usually considered the criterion for a positive Ames test.
Reproductive and Developmental Toxicology
Dorzolamide Hydrochloride
In reproduction studies of dorzolamide hydrochloride in rats, there were no adverse effects on males or females at doses up to 188 or 94 times, respectively, the maximum recommended human ophthalmic dose.
There were no treatment-related fetal malformations in developmental toxicity studies with dorzolamide hydrochloride in rats at oral doses up to 10 mg/kg/day (125 times the maximum recommended human ophthalmic dose). Developmental toxicity studies with dorzolamide hydrochloride in rabbits at oral doses of ≥ 2.5 mg/kg/day (31 times the maximum recommended human ophthalmic dose) revealed malformations of the vertebral bodies. These malformations occurred only at doses that caused metabolic acidosis with resultant decreased body weight gain in dams and decreased fetal weights. These malformations, seen only at maternotoxic doses, appear to be a class-effect related to a combination of electrolyte and acid-base changes: decreased venous HCO3-, decreased venous pH and decreased serum potassium. No treatment-related malformations were seen at 1.0 mg/kg/day (13 times the maximum recommended human ophthalmic dose). Acetazolamide, an oral CAI, causes skeletal malformations in rats and rabbits by a similar mechanism.
In a study of dorzolamide hydrochloride in lactating rats, decreases in body weight gain of 5 to 7% in offspring at an oral dose of 7.5 mg/kg/day (94 times the maximum recommended human ophthalmic dose) were seen during lactation. A slight delay in postnatal development (incisor eruption, vaginal canalization and eye openings), secondary to lower fetal body weight, was noted at 7.5 mg/kg/day (94 times the maximum recommended human ophthalmic dose).
Timolol Maleate
Reproduction and fertility studies in rats showed no adverse effect on male or female fertility at doses up to 150 times the maximum recommended human oral dose.
Teratogenicity studies with timolol in mice and rabbits at doses up to 50 mg/kg/day (50 times the maximum recommended human oral dose) showed no evidence of fetal malformations.
Although delayed fetal ossification was observed at this dose in rats, there were no adverse effects on postnatal development of offspring. Doses of 1000 mg/kg/day (1000 times the maximum recommended human oral dose) were maternotoxic in mice and resulted in an increased number of fetal resorptions. Increased fetal resorptions were also seen in rabbits at doses of 100 times the maximum recommended human oral dose, in this case without apparent maternotoxicity.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. COSOPT® (dorzolamide and timolol ophthalmic Solution, 20 mg/mL dorzolamide hydrochloride and 5 mg/mL timolol maleate, submission control number 259275, Product Monograph, Elvium Life Sciences. (May 24, 2022)