


Product Monograph - Effexor Tablets, 75mg
ACTIONS AND CLINICAL PHARMACOLOGY
Venlafaxine is a phenethylamine bicyclic derivative, chemically unrelated to tricyclic, tetracyclic or other available antidepressant or anxiolytic agents.
Pharmacodynamics
The mechanism of venlafaxine's antidepressant action in humans is believed to be associated with its potentiation of neurotransmitter activity in the CNS. Preclinical studies have shown that venlafaxine and its active metabolite, O-desmethylvenlafaxine (ODV), are potent inhibitors of neuronal serotonin and norepinephrine reuptake and weak inhibitors of dopamine reuptake.
Venlafaxine and ODV have no significant affinity for muscarinic, histaminergic, or "1-adrenergic receptors in vitro. Pharmacologic activity at these receptors is hypothesized to be associated with the various anticholinergic, sedative, and cardiovascular effects seen with other psychotropic drugs. Venlafaxine and ODV do not possess monoamine oxidase (MAO) inhibitory activity.
Pharmacokinetics
EFFEXOR Tablets
Venlafaxine is well absorbed, with peak plasma concentrations occurring approximately 2 hours after dosing. Venlafaxine is extensively metabolized, with O-desmethylvenlafaxine, (ODV, the only major active metabolite) peak plasma levels occurring approximately 4 hours after dosing.
Following single doses of 25 to 75 mg, mean (± SD) peak plasma concentrations of venlafaxine range from 37 ± 14 to 102 ± 41 ng/mL, respectively, and are reached in 2 ± 1 hours, and mean peak ODV plasma concentrations range from 61 ± 13 to 168 ± 37 ng/mL and are reached in 4 ±
2 hours. Approximately 87% of a single dose of venlafaxine is recovered in the urine within 48 hours as either unchanged venlafaxine (5%), unconjugated ODV (29%), conjugated ODV (26%), or other minor inactive metabolites (27%), and 92% of the radioactive dose is recovered within
72 hours. Therefore, renal elimination of venlafaxine and its metabolites is the primary route of excretion.
EFFEXOR XR Capsules
After administration of EFFEXOR XR (venlafaxine hydrochloride, extended release capsules), the peak plasma concentrations of venlafaxine and ODV are attained within 6.0±1.5 and 8.8±2.2 hours, respectively. The rate of absorption of venlafaxine from the EFFEXOR XR capsule is slower than its rate of elimination. Therefore, the apparent elimination half-life of venlafaxine following administration of EFFEXOR® XR (15±6 hours) is actually the absorption half-life instead of the true disposition half-life (5±2) hours observed following administration of an
EFFEXOR® (venlafaxine hydrochloride) immediate release tablet.
Multiple-Dose Pharmacokinetic Profile (Tablets and Extended Release Capsules)
Steady-state concentrations of both venlafaxine and ODV in plasma are attained within 3 days of oral multiple dose therapy. The clearance of venlafaxine is slightly (15%) lower following multiple doses than following a single dose.
Venlafaxine and ODV exhibited approximately linear kinetics over the dose range of 75 to 450 mg/day.
The mean±SD steady-state plasma clearances of venlafaxine and ODV are 1.3±0.6 and 0.4±0.2
L/h/kg, respectively; apparent elimination half-life is 5±2 and 11±2 hours, respectively; and apparent (steady-state) volume of distribution is 7.5±3.7 and 5.7±1.8 L/kg, respectively.
Venlafaxine and ODV renal clearances are 49 ± 27 and 94 ± 56 mL/h/kg, respectively, which correspond to 5 ± 3.0% and 25 ± 13% of an administered venlafaxine dose recovered in urine as venlafaxine and ODV, respectively.
When equal daily doses of venlafaxine were administered as either an immediate release tablet or the extended release capsule, the exposure (AUC, area under the concentration curve) to both venlafaxine and ODV was similar for the two treatments, and the fluctuation in plasma concentrations was slightly lower following treatment with the extended release capsule.
Therefore, the EFFEXOR XR capsules provide a slower rate of absorption, but the same extent of absorption (i.e., AUC), as the venlafaxine immediate release tablet.
Results of testing in healthy volunteers demonstrated differences in the gastrointestinal tolerability of different formulations of venlafaxine. Data from healthy volunteers showed reduced incidence and severity of nausea with EFFEXOR XR capsules, compared with
EFFEXOR immediate release tablets.
Venlafaxine and ODV are 27 and 30% bound to human plasma proteins, respectively.
Therefore, administration of venlafaxine to a patient taking another drug that is highly protein-bound should not cause increased free concentrations of the other drug. Following intravenous administration, the steady-state volume of distribution of venlafaxine is 4.4±1.9L/kg, indicating that venlafaxine distributes well beyond the total body water.
Following absorption, venlafaxine undergoes extensive presystemic metabolism in the liver. On the basis of mass balance studies, at least 92% of a single dose of venlafaxine is absorbed. The absolute bioavailability of venlafaxine is approximately 45%. The primary metabolite of venlafaxine is ODV, which is an active metabolite. Venlafaxine is also metabolized to N-desmethylvenlafaxine, N,O-didesmethylvenlafaxine, and other minor metabolites. In vitro studies indicate that the formation of ODV is catalysed by CYP2D6 and that the formation of N-desmethylvenlafaxine is catalysed by CYP3A3/4. The results of the in vitro studies have been confirmed in a clinical study with subjects who are CYP2D6 poor and extensive metabolizers.
However, despite the metabolic differences between the CYP2D6 poor and extensive metabolizers, the total exposure to the sum of the two active species (venlafaxine and ODV, which have comparable activity) was similar in the two metabolizer groups.
Food has no significant effect on the absorption of venlafaxine or on the subsequent formation of
ODV.
Age and Gender
Population pharmacokinetic analyses of 547 venlafaxine-treated patients from three studies involving both venlafaxine immediate release tablets and venlafaxine extended release capsules showed that age and sex do not significantly affect the pharmacokinetics of venlafaxine. A 20% reduction in clearance was noted for ODV in subjects over 60 years old; this was possibly caused by the decrease in renal function that typically occurs with aging. Dosage adjustment based upon age or gender is generally not necessary (See DOSAGE AND ADMINISTRATION).
Extensive/Poor Metabolizers
Plasma concentrations of venlafaxine were higher in CYP2D6 poor metabolizers than extensive metabolizers. Because the total exposure (AUC) of venlafaxine and ODV was similar in poor and extensive metabolizer groups, there is no need for different venlafaxine dosing regimens for these two groups.
Hepatic Disease
In 9 patients with hepatic cirrhosis, the pharmacokinetic disposition of both venlafaxine and
ODV was significantly altered. Venlafaxine elimination half-life was prolonged by about 30%, and clearance was decreased by about 50% in cirrhotic patients compared to normal subjects.
ODV elimination half-life was prolonged by about 60% and clearance decreased by about 30% in cirrhotic patients compared to normal subjects.
A large degree of intersubject variability was noted. Three patients with more severe cirrhosis had a more substantial decrease in venlafaxine clearance (about 90%) compared to normal subjects. Dosage adjustment is necessary in patients with liver disease (See DOSAGE AND
ADMINISTRATION).
Renal Disease
In patients with moderate to severe impairment of renal function (GFR = 10-70 mL/min), venlafaxine elimination half-life was prolonged by 50%, and clearance was deceased by about
24% compared to normal subjects. ODV elimination half-life was prolonged by about 40%, but clearance was unchanged.
In dialysis patients, venlafaxine elimination half-life was prolonged by about 180% and clearance was decreased by about 57%. In dialysis patients, ODV elimination half-life was prolonged by about 142%, and clearance was reduced by about 56% compared to normal subjects.
A large degree of intersubject variability was noted.
Dosage adjustment is necessary in patients with renal disease (See DOSAGE AND
ADMINISTRATION).
Clinical Trials
DEPRESSION
EFFEXOR Tablets (Immediate release)
The efficacy of EFFEXOR tablets in the treatment of depression was established in 6-week controlled trials of outpatients whose diagnoses corresponded most closely to the DSM-II or
DSM-III-R category of major depressive disorder and in a 4-week controlled trial of inpatients meeting diagnostic criteria for major depressive disorder with melancholia.
In one longer term study, outpatients meeting DSM-III-R criteria for major depressive disorder, recurrent type, who had “responded”* during an initial 26 weeks of treatment on EFFEXOR
(100 to 200 mg/day, on a b.i.d. schedule) and continued to be “improved”*, were randomized to continuation of their same EFFEXOR dose or to placebo. The follow-up period to observe patients for “relapse”* was for up to 52 weeks. Patients receiving continued EFFEXOR treatment experienced significantly lower relapse rates over the subsequent 52 weeks compared with those receiving placebo.
*For the purposes of this study:
“Responded” was defined as HAM-D-21 total score # 12 at the day 56 evaluation)
“Improved” was defined as the following criteria being met for days 56 through 180: (1) no
HAM-D-21 total score $20; (2) no more than 2 HAM-D-21 total scores >10, and (3) no single
CGI Severity of Illness item score $4 (moderately ill).
“Relapse” was defined as a CGI Severity of Illness item score $4 during the double-blind phase.
EFFEXOR XR Capsules (Extended release)
The efficacy of EFFEXOR XR (venlafaxine hydrochloride extended release) capsules as a treatment for depression was established in two placebo-controlled, short-term, flexible-dose studies in adult outpatients meeting DSM-III-R or DSM-IV criteria for major depression. An 8-week study utilizing EFFEXOR XR doses in a range 75-225 mg/day (mean dose for completers was 177 mg/day) and a 12-week study utilizing EFFEXOR XR doses in a range 75-150 mg/day
(mean dose for completers was 136 mg/day). The 12-week study also compared EFFEXOR XR to EFFEXOR Tablets. Both studies demonstrated superiority of EFFEXOR XR over placebo on the HAM-D total score, the HAM-D Depressed Mood Item, the MADRS total score, the CGI
Severity of illness scale, and the CGI Global Improvement scale. In both studies, EFFEXOR XR was also significantly better than placebo for certain factors of the HAM-D, including the anxiety/somatization factor, the cognitive disturbance factor, and the retardation factor, as well as for the psychic anxiety score.
In the 12-week study comparing EFFEXOR tablets with EFFEXOR XR capsules, once daily,
EFFEXOR XR was significantly more effective at weeks 8 and 12, compared with EFFEXOR tablets given twice daily for treating major depression. Analysis of safety data from this trial showed that the incidence of treatment-emergent nausea and nausea severity over time were lower with EFFEXOR XR than with EFFEXOR tablets. Additionally, the incidence of vomiting was lower with EFFEXOR XR than with EFFEXOR.
In one longer term study, outpatients meeting DSM-IV criteria for major depressive disorder who had “responded”* during an 8-week open trial on EFFEXOR XR capsules (75, 150, or 225 mg, in the morning (qAM) were randomized to continuation of their same EFFEXOR XR dose or to placebo, for up to 26 weeks of observation for “relapse”*. Patients receiving continued
EFFEXOR XR treatment experienced significantly lower “relapse”* rates compared with those on placebo.
*For the purposes of this study:
“Responded” during the open phase was defined as a CGI Severity of Illness item score # 3 and a HAM-D-21 total score of# 10 at the day 56 evaluation.
“Relapse” during the double-blind phase was defined as follows:
(1) a reappearance of major depressive disorder as defined by DSM-IV criteria and a CGI
Severity of Illness item score of $ 4 (moderately ill),
(2) 2 consecutive CGI Severity of Illness item scores of $ 4, or
(3) a final CGI Severity of Illness item score of $4 for any patient who withdrew from the study for any reason.
Generalized Anxiety Disorder (GAD)
The efficacy of EFFEXOR XR capsules in the treatment of GAD has been demonstrated in three fixed dose studies and one flexible dose study for time periods ranging from 8 to 28 weeks.
In these studies, EFFEXOR XR was shown to have a statistically significant superiority over placebo on the following three measures: Hamilton Anxiety Rating Scale (total score), Hamilton anxious mood item, and Clinical Global Impression of Severity of Illness rating.
In the three fixed dose studies, response rates at week 8 of treatment, as defined by the proportion of patients achieving Clinical Global Impression of Improvement Scores of “much”
or “very much improved”, were as follows (last observation carried forward):
| Study # | Placebo | 37.5 mg | 75.0 mg | 150 mg | 225 mg | |||||
| N | % | N | % | N | % | N | % | N | % | |
| 210 US | 96 | 49% | 86 | 57% | 81 | 58% | 86 | 65% | ||
| 378 EU | 130 | 45% | 138 | 59% | 130 | 69% | 131 | 78% | ||
| 214 US | 98 | 39% | 87 | 62% | 87 | 49% | ||||
For the two long-term studies, response rates at month 6 were as follows for last observation carried forward (LOCF):
| Study # | Placebo | 37.5 mg | 75.0 mg | 150 mg | 75-225 mg | ||||||
| N | % | N | % | N | % | N | % | N | % | ||
| 378 EU | LOCF | 123 | 33% | 115 | 67% | ||||||
| 218 US | LOCF | 130 | 48% | 138 | 66% | 130 | 75% | 131 | 81% | ||
Social Anxiety Disorder (Social Phobia)
The efficacy of EFFEXOR XR capsules as a treatment for Social Anxiety Disorder (also known as Social Phobia) was established in two 12-week, multicenter, placebo-controlled, flexible-dose studies in adult outpatients meeting DSM-IV criteria for Social Anxiety Disorder. These studies evaluating EFFEXOR XR doses in a range of 75-225 mg/day demonstrated that EFFEXOR XR was significantly more effective than placebo for the Liebowitz Social Anxiety Scale Total score.
Examination of subsets of the population studied did not reveal any differential responsiveness on the basis of age or gender.
INDICATIONS AND CLINICAL USE
DEPRESSION:
EFFEXOR® Tablets (immediate release) and EFFEXOR XR Capsules (extended release) are indicated for the symptomatic relief of major depressive disorder.
The short-term efficacy of EFFEXOR Tablets (immediate release) has been demonstrated in placebo controlled trials of up to 6 weeks.
The short-term efficacy of EFFEXOR XR Capsules (extended release) has been demonstrated in placebo controlled trials of up to 12 weeks.
The efficacy of EFFEXOR Tablets (immediate release) in maintaining an antidepressant response in patients with recurrent depression was demonstrated in a 52 week placebo-controlled trial (see “Clinical Trials”).
The efficacy of EFFEXOR XR Capsules (extended release) in maintaining an antidepressant response for up to 26 weeks following response to 8 weeks of acute treatment was demonstrated in a placebo-controlled trial (see “Clinical Trials”).
GENERALIZED ANXIETY DISORDER (GAD):
EFFEXOR XR Capsules are indicated for the symptomatic relief of anxiety causing clinically significant distress in patients with GAD. Anxiety or tension associated with the stress of everyday life usually does not require treatment with an anxiolytic. The effectiveness of
EFFEXOR XR in long-term use has been evaluated for up to 6 months in controlled clinical trials.
SOCIAL ANXIETY DISORDER (SOCIAL PHOBIA):
EFFEXOR XR is indicated for the symptomatic relief of Social Anxiety Disorder, also known as
Social Phobia.
Social Anxiety Disorder is characterized by a marked and persistent fear of one or more social or performance situations, in which the person is exposed to unfamiliar people or to possible scrutiny by others. Exposure to the feared situation almost invariably provokes anxiety, which may approach the intensity of a panic attack. The feared situations are avoided or endured with intense anxiety or distress. Fear, anxious anticipation, distress in the feared situation(s) or avoidance of social and/or performance situations that does not interfere significantly with the person's normal routine, occupational or academic functioning, or social life usually does not require treatment with an anxiolytic.
The physician who elects to use EFFEXOR or EFFEXOR XR for extended periods in the treatment of depression, GAD, or Social Anxiety Disorder should periodically re-evaluate the long-term usefulness of the drug for the individual patient (See “DOSAGE AND
ADMINISTRATION”).
CONTRAINDICATIONS
Hypersensitivity
EFFEXOR/EFFEXOR XR (venlafaxine HCl) Tablets/Capsules are contraindicated in patients with known hypersensitivity to venlafaxine or to any of the components of the formulations. Monoamine Oxidase Inhibitors (MAOIs):
EFFEXOR/EFFEXOR XR should not be used in combination with MAOIs or within two weeks of terminating treatment with MAOIs. Treatment with MAOIs should not be started until 2 weeks after discontinuation of EFFEXOR/EFFEXOR XR therapy.
Adverse reactions, some serious, have been reported when EFFEXOR/EFFEXOR XR therapy is initiated soon after discontinuing an MAOI and when an MAOI is initiated soon after discontinuation of EFFEXOR/EFFEXOR XR. These reactions have included tremor, myoclonus, diaphoresis, nausea, vomiting, flushing, dizziness, hyperthermia with features resembling neuroleptic malignant syndrome, seizures and death. In patients receiving antidepressants with pharmacological properties similar to venlafaxine in combination with an
MAOI, there have also been reports of serious, sometimes fatal, reactions. For a selective serotonin reuptake inhibitor, these reactions have included hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes that include extreme agitation progressing to delirium and coma. Some cases presented with features resembling neuroleptic malignant syndrome. Severe hypothermia and seizures, sometimes fatal, have been reported in association with the combined use of tricyclic antidepressants and MAOIs. These reactions have also been reported in patients who have recently discontinued these drugs and have been started on an MAOI.
WARNINGS
POTENTIAL ASSOCIATION WITH BEHAVIOURAL AND EMOTIONAL CHANGES,
INCLUDING SELF-HARM.
Pediatrics: Placebo-Controlled Clinical Trial Data
- Recent analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer anti-depressants suggest that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo.
- The small denominators in the clinical trial database, as well as the variability in placebo rates, preclude reliable conclusions on the relative safety profiles among the drugs in the class.
Adults and Pediatrics: Additional data
There are clinical trial and post-marketing reports with SSRIs and other newer anti-depressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm or harm to others. The agitation-type events include:
akathisia, agitation, disinhibition, emotional lability, hostility, aggression, depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages. This includes monitoring for agitation-type emotional and behavioural changes.
Discontinuation
Patients currently taking EFFEXOR/EFFEXOR XR should NOT be discontinued abruptly, due to risk of discontinuation symptoms (See PRECAUTIONS). At the time that a medical decision is made to discontinue an SSRI or other newer antidepressant drug, a gradual reduction in the dose, rather than an abrupt cessation, is recommended.
Sustained Hypertension
EFFEXOR Tablets
Sustained increases in blood pressure could have adverse consequences. Therefore, it is recommended that patients receiving venlafaxine have their blood pressure monitored regularly.
For patients who experience a sustained increase in blood pressure while receiving venlafaxine, either dose reduction or discontinuation should be considered after a benefit-risk assessment is made.
Treatment with EFFEXOR (venlafaxine HCl) Tablets was associated with modest but sustained increases in blood pressure during premarketing studies. Sustained hypertension, defined as treatment-emergent supine diastolic blood pressure (SDBP) $ 90 mm Hg and $ 10 mm Hg above baseline for 3 consecutive visits, showed the following incidence and dose-relationship: TABLE 1 : PROBABILITY OF SUSTAINED ELEVATION IN SDBP
Probability of Sustained Elevation in SDBP (Pool of Premarketing Depression Studies with EFFEXOR/EFFEXOR XR) | |
| Treatment Group | (%) Incidence of Sustained Elevation in SDBP |
| Venlafaxine | Immediate Release Extended Release EFFEXOR EFFEXOR XR |
| < 100 mg/day | 2 3 |
| 101-200 mg/day | 5 2 |
| 201-300 mg/day | 6 4 |
| > 300 mg/day | 13 NE* |
| Placebo | 2 0 |
* Not evaluable
An analysis of the blood pressure increases in patients with sustained hypertension and in the 19 patients who were discontinued from treatment because of hypertension (<1% of total venlafaxine-treated group) showed that most of the blood pressure increases were in the range of
10 to 15 mm Hg, SDBP.
EFFEXOR XR Capsules
Depression: In placebo-controlled premarketing depression studies with EFFEXOR XR, a final on-therapy mean increase in supine diastolic pressure (SDBP) of < 1.2 mm Hg was observed for
EFFEXOR XR-treated patients compared with a mean decrease of 0.2 mm Hg for placebo-treated patients. Less than 3% of EFFEXOR XR patients treated with doses of 75 to 300 mg/day had sustained elevations in blood pressure (defined as treatment-emergent SDBP $90 mm Hg and $10 mm Hg above baseline for 3 consecutive on-therapy visits). An insufficient number of patients received doses of EFFEXOR XR >300 mg/day to evaluate systematically sustained blood pressure increases. Less than 1% of EFFEXOR XR-treated patients in double-blind, placebo-controlled premarketing depression studies discontinued treatment because of elevated blood pressure compared with 0.4% of placebo-treated patients.
GAD: In placebo-controlled premarketing anxiety studies with EFFEXOR XR 37.5-225 mg/day, a final on-drug mean increase in SDBP of 0.4 mm Hg was observed for EFFEXOR XR treated patients compared with a mean decrease of 0.8 mm Hg for placebo treated patients.
Social Anxiety Disorder (Social Phobia): In placebo-controlled premarketing Social Anxiety
Disorder studies with EFFEXOR XR 75-225 mg/day up to 12 weeks, a final on-drug mean increase in SDBP of 1.6 mm Hg was observed for EFFEXOR XR-treated patients compared with a mean decrease of 1.1 mm Hg for placebo-treated patients.
Among patients treated with 75-225 mg per day of EFFEXOR XR in premarketing Social
Anxiety Disorder studies, 1.4% (4/277) experienced sustained hypertension.
In premarketing Social Anxiety Disorder studies up to 12 weeks with patients treated with 75-
225 mg per day, 0.4% (1/277) of the EFFEXOR XR-treated patients discontinued treatment because of elevated blood pressure. In this patient, the blood pressure increase was modest (13 mm Hg, SDBP).
PRECAUTIONS
General
Suicide
The possibility of a suicide attempt in depressed patients is inherent to the illness and may persist until significant remission occurs. Close supervision of patients should accompany initial drug therapy, and consideration should be given to the need for hospitalization of high risk patients. In order to reduce the risk of overdose, prescriptions for EFFEXOR/EFFEXOR XR
(venlafaxine HCl) Tablets/Capsules should be written for the smallest quantity of
tablets/capsules consistent with good patient management.
The same precautions observed when treating patients with depression should be observed when treating patients with GAD or Social Anxiety Disorder. (See WARNINGS: POTENTIAL
ASSOCIATION WITH BEHAVIOURAL AND EMOTIONAL CHANGES, INCLUDING
SELF-HARM.)
Seizures
EFFEXOR/EFFEXOR XR should be used cautiously in patients with a history of seizures, and should be promptly discontinued in any patient who develops seizures. Seizures have also been reported as a discontinuation symptom (see also PRECAUTIONS, Discontinuation Symptoms: ADVERSE EVENTS, Discontinuation Symptoms; DOSAGE AND ADMINISTRATION,
Discontinuing Venlafaxine).
During premarketing testing, seizures were reported in 8 out of 3,082 EFFEXOR Tablet-treated patients (0.26%). In 5 of the 8 cases with immediate release tablets, patients were receiving doses of 150 mg/day or less. During premarketing depression studies no seizures were seen in
705 EFFEXOR XR Capsule-treated patients. Premarketing, no seizures occurred among 1381
EFFEXOR XR-treated patients in Generalized Anxiety Disorder studies or among 277
EFFEXOR XR-treated patients in Social Anxiety Disorder Studies. However, patients with a history of convulsive disorders were excluded from most of these studies. EFFEXOR/
EFFEXOR XR should be used cautiously in patients with a history of seizures, and should be promptly discontinued in any patient who develops seizures.
Serum Cholesterol Elevation
Clinically relevant increases in total serum cholesterol were recorded in 5.3% of venlafaxine-treated patients and 0.0% of placebo-treated patients treated for at least 3 months in placebo-controlled trials in Major Depressive Disorders. (see ADVERSE REACTIONS–Laboratory
Changes).
Consistent with the above findings, elevations of High Density Lipoprotein Cholesterol (HDL),
Low Density Lipoprotein Cholesterol (LDL) and the overall ratio of Total Cholesterol/HDL have been observed in placebo controlled clinical trials for Social Anxiety Disorder (SAD). Measurement of serum cholesterol levels (including a complete lipid profile/fractionation and an assessment of the patient’s individual risk factors) should be considered especially during long-term treatment.
Abnormal Bleeding
There have been reports of abnormal bleeding (most commonly ecchymosis) associated with venlafaxine treatment. While a causal relationship to venlafaxine is unclear, impaired platelet aggregation may result from platelet serotonin depletion and contribute to such occurrences.
Skin and other mucous membrane bleedings have been reported following treatment with venlafaxine. Venlafaxine should therefore be used with caution in patients concomitantly treated with drugs that give an increased risk for bleeding (e.g. anticoagulants, nonsteroidal anti-inflammatories and ASA) and in patients with a known tendency for bleeding or those with predisposing conditions.
Discontinuation Symptoms
Discontinuation symptoms have been assessed both in patients with depression and those with anxiety. Abrupt discontinuation, dose reduction, or tapering of venlafaxine at various doses has been found to be associated with the appearance of new symptoms, the frequency of which increased with increased dose level and with longer duration of treatment. If venlafaxine is used until or shortly before birth, discontinuation effects in the newborn should be considered. Reported symptoms include anorexia, anxiety, agitation, confusion, convulsions, coordination impaired, diarrhea, dizziness, dry mouth, dysphoric mood, fasciculation, fatigue, headache, hypomania, insomnia, nausea, nervousness, nightmares, paresthesia, electric shock sensations, sensory disturbances (including shock like electrical sensations), sleep disturbances, somnolence, sweating, tinnitus, vertigo, and vomiting. Where such symptoms occurred they were usually self-limiting but in a few patients continued for several weeks.
Discontinuation effects are well known to occur with antidepressants, and, therefore, it is recommended that the dosage be tapered gradually and the patient monitored (See DOSAGE
AND ADMINISTRATION).
Activation of Mania/Hypomania
During Phase II and III trials, mania or hypomania occurred in 0.5% of EFFEXOR Tablet-treated patients and in 0.3% and 0% of EFFEXOR XR Capsule-treated patients in depression and anxiety studies respectively. In premarketing Social Anxiety Disorder studies, no
EFFEXOR XR-treated patients and no placebo-treated patients experienced mania or hypomania. Mania or hypomania occurred in 0.5% of all venlafaxine-treated patients.
Mania/hypomania has also been reported in a small proportion of patients with major affective disorder who were treated with other marketed antidepressants. As with all antidepressants,
EFFEXOR/EFFEXOR XR should be used cautiously in patients with a history of mania.
Allergic Reactions
Patients should be advised to notify their physician if they develop a rash, hives or a related allergic phenomenon.
Hyponatremia
As with some other antidepressants, several cases of hyponatremia have been reported with
EFFEXOR®, usually in volume-depleted or dehydrated patients including those taking diuretics.
The hyponatremia appeared to be reversible when EFFEXOR was discontinued. The majority of these occurrences have been in the elderly individuals.
Inappropriate Antidiuretic Hormone Secretion
Rare events of Syndrome of Inappropriate Antidiuretic Hormone (SIADH) secretion have been reported, usually in volume-depleted or dehydrated patients including elderly patients and patients taking diuretics, treated with EFFEXOR. Although the reported events occurred coincident with treatment with EFFEXOR, the relationship to treatment is unknown.
Use in Patients with Concomitant Illness
Clinical experience with venlafaxine in patients with concomitant systemic illness is limited.
Caution is advised in administering venlafaxine to patients with diseases or conditions that could affect hemodynamic responses or metabolism. Patients should be questioned about any prescription or "over the counter drugs, herbal or natural products or dietary supplements" that they are taking, or planning to take, since there is a potential for interactions. ! Cardiac Disease
Venlafaxine has not been evaluated or used to any appreciable extent in patients with a recent history of myocardial infarction or unstable heart disease. Patients with these diagnoses were systematically excluded from many clinical studies during the product's clinical trials. Therefore it should be used with caution in these patients. Evaluation of the electrocardiograms for 769 patients who received venlafaxine immediate release tablets in 4- to 6-week double-blind trials showed that the incidence of trial-emergent conduction abnormalities did not differ from that with placebo.
The electrocardiograms for 357 patients who received EFFEXOR XR and 285 patients who received placebo in 8 to 12 week double-blind, placebo-controlled trials in depression were analyzed. The mean change from baseline in corrected QT interval
(QTc) for EFFEXOR XR-treated patients in depression studies was increased relative to that for placebo-treated patients (increase of 4.7 msec for EFFEXOR XR and decrease of
1.9 msec for placebo). The clinical significance of this change is unknown. Three of 705
EFFEXOR XR-treated patients in phase III studies experienced QTc prolongation to 500 msec during treatment. Baseline QTc was >450 msec for all 3 patients.
Electrocardiograms are available for 815 patients who received EFFEXOR XR and 379 patients who received placebo in up to 6-month, double-blind, placebo-controlled trials in generalized anxiety disorder. The mean change from baseline in the corrected QT interval (QTc) for EFFEXOR XR-treated patients in the GAD studies did not differ significantly from that with placebo. One of the 815 EFFEXOR XR-treated patients experienced QTc prolongation to 593 msec. Baseline QTc was 460 msec for this one patient.
Electrocardiograms were evaluated for 277 patients who received EFFEXOR XR and
274 patients who received placebo in 12-week double-blind, placebo-controlled trials in
Social Anxiety Disorder. The mean change from baseline in QTc for EFFEXOR XR-treated patients in the Social Anxiety Disorder studies was increased relative to that for placebo-treated patients (increase of 2.8 msec for EFFEXOR XR and decrease of 2.0 msec for placebo).
No case of sudden unexplained death or serious ventricular arrhythmia, which are possible clinical sequelae of QTc prolongation, was reported in EFFEXOR XR pre-marketing studies.
The mean heart rate was increased by about 3-4 beats per minute during treatment with
EFFEXOR and EFFEXOR XR in clinical trials of depression and GAD. The mean change from baseline in heart rate for EFFEXOR XR-treated patients in the Social
Anxiety Disorder studies was significantly higher than that for placebo (a mean increase of 5 beats per minute for EFFEXOR XR and no change for placebo). Increases in heart rate can occur, particularly with higher doses. Caution should be exercised in patients whose underlying conditions might be compromised by increases in heart rate.
Venlafaxine treatment has been associated with sustained hypertension (see
WARNINGS).
! Hepatic and Renal Disease
In patients with hepatic or renal impairment (GFR=10-70 mL/min), the pharmacokinetic disposition of both venlafaxine and the active metabolite ODV are significantly altered.
Dosage adjustment is necessary in these patients (See DOSAGE AND
ADMINISTRATION).
Insomnia and Nervousness
Treatment-emergent insomnia and nervousness were more commonly reported for patients treated with EFFEXOR and EFFEXOR XR than with placebo (see ADVERSE REACTIONS)
in depression, GAD, and Social Anxiety Disorder studies, as shown in Table 1.
Table 1
Incidence of Insomnia and Nervousness in Placebo-Controlled Depression, GAD,
and Social Anxiety Disorder Trials Depression GAD Social Anxiety Disorder
Symptom
EFFEXOR XR
n = 357
Placebo
n = 285
EFFEXOR XR
n = 1381
Placebo
n = 555
EFFEXOR XR n = 277
Placebo n=274
Insomnia 17% 11% 15% 10% 23% 7% Nervousness 10% 5% 6% 4% 11% 3%
Insomnia and nervousness each led to drug discontinuation in 0.9% of the patients treated with
EFFEXOR XR in depression studies.
In GAD trials, insomnia and nervousness led to drug discontinuation in 3% and 2%, respectively, of the patients treated with EFFEXOR XR up to 8 weeks and 2% and 0.7%, respectively, of the patients treated with EFFEXOR XR up to 6 months. In Social Anxiety
Disorder trials, insomnia and nervousness led to drug discontinuation in 3% and 0%, respectively, of the patients treated with EFFEXOR XR up to 12 weeks.
Changes in Appetite and Weight
Treatment-emergent anorexia and weight loss were more commonly reported for EFFEXOR and
EFFEXOR XR-treated patients than for placebo-treated patients in depression and GAD and
Social Anxiety Disorder trials. Significant weight loss, especially in underweight depressed/GAD patients, may be an undesirable result of treatment. EFFEXOR or EFFEXOR
XR are not recommended for weight loss alone or in combination with other products such as phentermine or sibutramine. Based on the known mechanisms of action, the potential harm of co-administration include the possibility of serotonin syndrome. (See PRECAUTIONS, Drug
Interactions, Serotonergic Drugs.)
Interference with Cognitive and Motor Performance
In healthy volunteers receiving EFFEXOR at a stable regimen of 150 mg/day, some impairment of psychomotor performance was observed. Patients should be cautioned about operating hazardous machinery, including automobiles, or engaging in tasks requiring alertness until they have been able to assess the drug’s effect on their own psychomotor performance.
Mydriasis
Mydriasis may occur in association with venlafaxine. It is recommended that patients with raised intra-ocular pressure or patients at risk for acute narrow-angle glaucoma be closely monitored.
Toxicology
The toxicologic profile of venlafaxine was evaluated for up to 18 months in mice, up to 2 years in rats, and up to 1 year in dogs. A single dose range finding study was done in monkeys. As part of its evaluation, the reproductive toxicologic potential of venlafaxine was evaluated in segment I, II, and III studies in rats and a segment II study in rabbits. The major findings in the acute, long term, and reproductive toxicity studies are discussed below.
Acute Toxicity
Venlafaxine showed low acute toxicity with LD50s $405 mg/kg in mice and $336 mg/kg in rats;
i.v. LD50s in mice were $48 mg/kg. No drug-related macroscopic lesions were observed;
microscopic examinations were not performed.
Long Term Toxicity/Carcinogenicity
Subchronic toxicity of venlafaxine was evaluated in mice, rats, dogs and monkeys (1-month range finding study only); chronic toxicity was evaluated in dogs; and chronic
toxicity/carcinogenicity was evaluated in mice and rats.
Mice
Venlafaxine was administered to mice for 3 months at 0, 24, 96, 138, 180
and 240 mg/kg to establish doses for a subsequent 18 month carcinogenicity study.
Drug-related tonic/clonic convulsions occurring in both 180 and 240 mg/kg groups were regarded as limiting for subsequent studies of longer duration due to anticipated mortality associated with convulsions of this magnitude. Based on these results, a maximum dose of 120 mg/kg was selected for chronic carcinogenicity studies which was regarded to provide a minimal margin below the convulsive threshold which would limit survival in a chronic study. In the 18 month study, mice were thus dosed at 10, 35, and 120 mg/kg. No carcinogenic effect was noted in males or females. A slight decrease in survival occurred in the 120 mg/kg males, but was not associated with specific microscopic lesions. The cause of death in the 120 mg/kg mice could not be clearly established. Male and female mice receiving 120 mg/kg were noted to have increased motor activity.
Rats
Rats were dosed with venlafaxine at 0, 4.5, 40, 170, and 340 mg/kg in the 6 month toxicity study and at 0, 10, 35, and 120 mg/kg in the 2 year study. No drug-related histologic lesions occurred in either study. In the six month study, an increased mortality was seen at 170 and 340 mg/kg.
Deaths were generally associated with convulsions. Effects noted included decreased body weight and food consumption at 170 and 340 mg/kg and increased incidence of physical examination findings at 40 mg/kg and above. Due to mortality, body weight, and food consumption effects, the maximum tolerated dose for the chronic study was considered to be below 170 mg/kg. The rat carcinogenicity study was conducted at dosages of 0, 10, 35, and 120 mg/kg for 2 years. As with the mouse, no carcinogenic effect was observed. An increased mortality was seen at 120 mg/kg; however, no clear drug-related lesion was associated with mortality. Mortality at lower dosages was comparable to historical limits (50-65%).
Dogs
In dogs, venlafaxine was administered for 6 months at 0, 2, 7, and 22 mg/kg and for 12 months at
0, 4, 10, and 24 mg/kg. As with the other species tested, no drug-related histologic lesions occurred. In the 6 month dog study, slightly decreased heart rate occurred in two dogs (during weeks 6, 12, 18, and 25 in one dog and week 25 in the other dog) receiving 22 mg/kg. Although effects on cardiovascular parameters have been seen with other antidepressants, including ECG alterations consisting of T wave changes (inversions, bifid T wave), prolongation of conduction and sinus tachycardia seen with tricyclic antidepressants, these effects were not seen after administration of venlafaxine. Blood pressure and ECGs were measured periodically throughout treatment at multiple intervals after ECG abnormalities in these or any other dogs in the 6 month or 1 year studies. A slight decrease in body weight gain was seen at the high dose in both studies. Mydriasis, a pharmacologic effect, occurred at all dosages. Other minor drug-related effects were generally limited to the high dose.
Monkeys
In monkeys, a range finding assay was conducted using one monkey/sex at dosages of 0, 25, 80,
125, 170, and 260 mg/kg for up to 27 days. Deaths occurred in the first 5 days in one of two monkeys at 125 mg/kg and all monkeys at higher dosages. No drug-related histologic changes were found in these animals, and deaths were considered secondary to drug-induced convulsions.
Electrocardiograms were only measured on the 80 mg/kg monkeys and showed no drug-related effects. Due to pharmacokinetic considerations, additional monkey studies were not conducted.
Mutagenicity
Venlafaxine and the major human metabolite, O-desmethylvenlafaxine (ODV), were not mutagenic in the Ames reverse mutation assay in Salmonella bacteria or the Chinese hamster ovary/HGPRT mammalian cell forward gene mutation assay. Venlafaxine was also not mutagenic or clastogenic in the in vitro BALB/c-3T3 mouse cell transformation assay, the sister chromatid exchange assay in cultured Chinese hamster ovary cells, or in the in vivo chromosomal aberration assay in rat bone marrow. ODV was not clastogenic in the in vitro
Chinese hamster ovary cell chromosomal aberration assay, but elicited a clastogenic response in the in vivo chromosomal aberration assay in rat bone marrow.
Reproductive Toxicity
The reproductive toxicology of venlafaxine was studied in rats and rabbits. No teratogenic effect was observed and no deaths occurred.
Pharmacotoxic signs were seen in paternal and maternal rats given venlafaxine doses of 30 and
60 mg/kg/day (4 and 8 times the maximum recommended human dose, respectively), but no adverse effect was noted in fertility or general reproductive performance. Decreased fetal size and pup weight at birth with 60 mg/kg/day may be correlated with maternal toxicity. In a perinatal toxicity study, decreased fetal survival following birth was observed at 40 and 80 mg/kg/day (approximately 5 to 11 times the maximum recommended human dose, respectively)
and was considered secondary to drug-related decreased maternal care. No teratogenic effect was seen. Evidence of carcinogenesis, mutagenesis, and impairment of fertility was not noted in preclinical toxicology studies.
Reproductive Toxicity with the Major Metabolite of Venlafaxine
Reduced fertility was observed in a study in which both male and female rats were exposed to the major metabolite of venlafaxine (ODV). This ODV exposure was approximately 2 to 3 times that which would result from a human dose of 225 mg/day of venlafaxine. The human relevance of this finding is unknown.
In this study, administration of ODV as the succinate salt in male and female rats resulted in disrupted estrous cycles and increased time-to-mating at $30 mg/kg/day; decreased fertility rates at $100 mg/kg/day; and increased preimplantation loss and decreased fetal weight at 300 mg/kg/day. There was decreased prostate weight at $30 mg/kg/day associated with prostate atrophy at $100 mg/kg/day; however, there were no compound-related macroscopic or microscopic findings in the epididymides, seminal vesicles, or testes. The no-observed-adverse-effect level (NOAEL) for effects on fertility was 30 mg/kg/day and the developmental NOAEL was 100 mg/kg/day.
Use in Pregnancy, Labour and Delivery, and in Nursing Mothers
There are no adequate and well controlled studies with venlafaxine in pregnant women.
Therefore, venlafaxine should only be used during pregnancy if clearly needed. Patients should be advised to notify their physician if they become pregnant or intend to become pregnant during therapy.
Post-marketing reports indicate that some neonates exposed to EFFEXOR or EFFEXOR XR,
SSRIs (Selective Serotonin Reuptake Inhibitors), or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and other newer antidepressants, or, possibly a drug discontinuation syndrome. It should be noted that, in some cases, the cliniccal picture is consistent with serotonin syndrome (see PRECAUTIONS - Drug Interactions - Serotonergic Drugs). When treating a pregnant woman with EFFEXOR or EFFEXOR XR during the third trimester, the physician should carefully consider the potential risks and benefits of treatment. (See DOSAGE
AND ADMINISTRATION).
Because venlafaxine and its active metabolite, O-desmethylvenlafaxine, have been reported to be excreted in human milk, lactating women should not nurse their infants while receiving venlafaxine. If the mother is taking EFFEXOR of EFFEXOR XR while nursing, the potential for discontinuation effects in the infant upon cessation of nursing should be considered.
Paediatric Use
Safety and efficacy in children below the age of 18 have not been established. Use in the Elderly
Of the 2,897 patients in Phase II and III trials with EFFEXOR Tablets, 357 (12%) were 65 years of age or older. Forty three (4%) of the patients in premarketing depression and 77 (6%) in
GAD trials respectively, with EFFEXOR XR Capsules, were 65 years of age or older. Six (2%)
patients in placebo-controlled Social Anxiety Disorder studies were 65 years or older. No overall differences in effectiveness and safety were observed between these geriatric patients and younger patients, and other reported clinical experience has not identified differences in response between the elderly and younger patients. However, greater sensitivity of some older individuals cannot be ruled out.
Drug Interactions
As with all drugs, the potential for interaction by a variety of mechanisms is a possibility.
! Lithium
The steady-state pharmacokinetics of venlafaxine 150 mg administered as 50 mg every 8 hours was not affected when a single 600 mg oral dose of lithium was administered to 12 healthy male subjects. ODV was also unaffected. Venlafaxine had no effect on the pharmacokinetics of lithium. (Also see Other CNS-Active Drugs.)
! Diazepam
The steady-state pharmacokinetics of venlafaxine 150 mg administered as 50 mg every 8 hours was not affected when a single 10 mg oral dose of diazepam was administered to
18 healthy male subjects. ODV was also unaffected. Venlafaxine had no effect on the pharmacokinetics of diazepam or its active metabolite, desmethyldiazepam.
Additionally, venlafaxine administration did not affect the psychomotor and psychometric effects induced by diazepam.
! Cimetidine
Concomitant administration of cimetidine and venlafaxine in a steady-state study for both drugs in 18 healthy male subjects resulted in inhibition of first-pass metabolism of venlafaxine. The oral clearance of venlafaxine was reduced by about 43%, and the exposure (AUC) and maximum concentration (Cmax) of the drug were increased by about
60%. However, there was no effect on the pharmacokinetics of ODV. The overall pharmacological activity of venlafaxine plus ODV is expected to increase only slightly, and no dosage adjustment should be necessary for most normal adults.
However, for patients with pre-existing hypertension, for elderly patients and for patients with hepatic or renal dysfunction, the interaction associated with the concomitant use of cimetidine and venlafaxine is not known and potentially could be more pronounced.
Therefore, caution is advised with such patients.
! Haloperidol
Venlafaxine administered under steady-state conditions at 150 mg/day in 24 healthy subjects decreased total oral-dose clearance (Cl/F) of a single 2 mg dose of haloperidol by 42%, which resulted in a 70% increase in haloperidol AUC. In addition, the haloperidol Cmax increased 88% when coadministered with venlafaxine, but the haloperidol elimination half-life (t½) was unchanged. The mechanism explaining this finding is unknown.
! Drugs Highly Bound to Plasma Proteins
Venlafaxine is not highly bound to plasma proteins; therefore, administration of venlafaxine to a patient taking another drug that is highly protein bound should not cause increased free concentrations of the other drug.
! Drugs that Inhibit Cytochrome P450 Isoenzymes
CYP2D6-Inhibitors:
In vitro and in vivo studies indicate that venlafaxine is metabolized to its active metabolite, ODV, by CYP2D6, the isoenzyme that is responsible for the genetic polymorphism seen in the metabolism of many antidepressants. Therefore, the potential exists for a drug interaction between drugs that inhibit CYP2D6 mediated metabolism and venlafaxine.
Drug interactions that reduce the metabolism of venlafaxine to ODV (see Imipramine below) potentially increase the plasma concentrations of venlafaxine and lower the concentrations of the active metabolite. However, the pharmacokinetic profile of venlafaxine in subjects concomitantly receiving a CYP2D6-inhibitor would not be substantially different than the pharmacokinetic profile in subjects who are CYP2D6 poor metabolizers, and no dosage adjustment is required.
CYP3A3/4 Inhibitors:
Because the two primary metabolic pathways for venlafaxine are through CYP2D6 and, to a lesser extent, CYP3A3/4, concomitant intake of inhibitors of both of these isoenzymes is not recommended during treatment with venlafaxine. Interactions between concomitant intake of inhibitors of both CYP2D6 and CYP3A3/4 with venlafaxine have not been studied.
In vitro studies indicate that venlafaxine is likely metabolized to a minor, less active metabolite, N-desmethylvenlafaxine, by CYP3A3/4. Because CYP3A3/4 is typically a minor pathway relative to CYP2D6 in the metabolism of venlafaxine, the potential for a clinically significant drug interaction between drugs that inhibit CYP3A3/4-mediated metabolism and venlafaxine is small.
! Drugs Metabolized by Cytochrome P450 Isoenzymes
CYP2D6
In vitro studies indicate that venlafaxine is a relatively weak inhibitor of CYP2D6. These findings have been confirmed in vivo by a clinical drug interaction study comparing the effect of venlafaxine with that of fluoxetine on the CYP2D6-mediated metabolism of dextromethorphan to dextrorphan.
Imipramine
Venlafaxine did not affect the pharmacokinetics of imipramine and 2-OH-imipramine.
However, AUC, Cmax and Cmin of desipramine (the active metabolite of imipramine)
increased by approximately 35% in the presence of venlafaxine. The 2-OH-desipramine
AUCs increased by at least 2.5 fold (with venlafaxine 37.5 mg q12h) and by 4.5 fold
(with venlafaxine 75 mg q12h). The clinical significance of elevated 2-OH-desipramine levels is unknown.
Imipramine partially inhibited the CYP2D6-mediated formation of ODV. However, the total concentration of active compounds (venlafaxine plus ODV) was not affected by coadministration with imipramine, and no dosage adjustment is required.
Risperidone
Venlafaxine administered under steady-state conditions at 150 mg/day slightly inhibited the CYP2D6-mediated metabolism of risperidone (administered as a single 1 mg oral dose) to its active metabolite, 9-hydroxyrisperidone, resulting in an approximate 32% increase in risperidone AUC. However, venlafaxine co-administration did not significantly alter the pharmacokinetic profile of the total active moiety (risperidone plus
9-hydroxyrisperidone).
CYP3A4
Venlafaxine did not inhibit CYP3A4 in vitro. This finding was confirmed in vivo by clinical drug interaction studies in which venlafaxine did not inhibit the metabolism of several CYP3A4 substrates, including alprazolam, diazepam, and terfenadine.
Indinavir
In a study of 9 healthy volunteers, venlafaxine administered under steady-state conditions at 150 mg/day resulted in a 28% decrease in the AUC of a single 800 mg oral dose of indinavir and a 36% decrease in indinavir Cmax. Indinavir did not affect the
pharmacokinetics of venlafaxine and ODV. The clinical significance of this finding is unknown.
CYP1A2
Venlafaxine did not inhibit CYP1A2 in vitro. This finding was confirmed in vivo by a clinical drug interaction study in which venlafaxine did not inhibit the metabolism of caffeine, a CYP1A2 substrate.
CYP2C9
Venlafaxine did not inhibit CYP2C9 in vitro. This finding was confirmed in vivo by a clinical drug interaction study in which venlafaxine did not inhibit the metabolism of tolbutamide, a CYP2C9 substrate.
CYP2C19
Venlafaxine did not inhibit the metabolism of diazepam, which is partially metabolized by CYP2C19 (see Diazepam above).
! Monoamine Oxidase Inhibitors: See “CONTRAINDICATIONS.”
! Other CNS-Active Drugs
The risk of using venlafaxine in combination with other CNS-active drugs has not been systematically evaluated. Consequently, caution is advised if the concomitant administration of venlafaxine and such drugs is required.
! Serotonergic Drugs
Based on the known mechanism of action of venlafaxine and the potential for serotonin syndrome, caution is advised when venlafaxine is co-administered with other drugs that may affect the serotonergic neurotransmitter systems (such as triptans, selective serotonin reuptake inhibitors, or lithium). Rare postmarketing reports describe patients with symptoms suggestive of, or diagnostic of, serotonin syndrome, following the combined use of a selective serotonin reuptake inhibitor (SSRI) with 5HT1-agonists (triptans) or lithium. If concomitant treatment with EFFEXOR/EFFEXOR XR and a triptan (e.g., almotriptan, sumatriptan, rizatriptan, naratriptan, zolmitriptan), tricyclic antidepressants, or other drugs with serotonergic activity (including but not limited to fenfluramine, tryptophan and silbutramine) is clinically warranted, appropriate observation of the patient for acute and long-term adverse events is advised. (See also PRECAUTIONS,
Changes in Appetite and Weight.)
! Alcohol
The possibility of additive psychomotor impairment should be considered if EFFEXOR is used in combination with alcohol. Patients should be advised to avoid alcohol while taking EFFEXOR.
! St. John’s Wort
In common with SSRI’s, pharmacodynamic interactions between
EFFEXOR/EFFEXOR XR and the herbal remedy St. John’s Wort may occur and may result in an increase in undesirable effects.
Postmarketing Reports
There have been reports of elevated clozapine levels that were temporally associated with adverse events including seizures, following the addition of venlafaxine. There have been reports of increases in prothrombin time, partial thromboplastin time, or INR when venlafaxine was given to patients receiving warfarin therapy.
Electroconvulsive Therapy
There are no clinical data on the use of electroconvulsive therapy combined with EFFEXOR or
EFFEXOR XR treatment.
Drug Abuse and Dependence
Physical and Psychological Dependence
In vitro studies revealed that venlafaxine has virtually no affinity for opiate, benzodiazepine, phencyclidine (PCP), or N-methyl-D-aspartic acid (NMDA) receptors. It has no significant CNS stimulant activity in rodents. In primate drug discrimination studies, venlafaxine showed no significant stimulant or depressant abuse liability.
While EFFEXOR/EFFEXOR XR have not been systematically studied in clinical trials for their potential for abuse, there was no indication of drug-seeking behavior in the clinical trials.
However, it is not possible to predict on the basis of premarketing experience the extent to which a CNS active drug will be misused, diverted, and/or abused once marketed. Consequently, physicians should carefully evaluate patients for history of drug abuse and follow such patients closely, observing them for signs of misuse or abuse of venlafaxine (e.g., development of tolerance, incrementation of dose, drug-seeking behavior).
ADVERSE REACTIONS
Commonly Observed Adverse Reactions
During depression trials, the most commonly observed adverse events associated with the use of
EFFEXOR and EFFEXOR XR (incidence of 5% or greater) and not seen at an equivalent incidence among placebo-treated patients (i.e., incidence for EFFEXOR/EFFEXOR XR at least twice that for placebo), derived from the 2% incidence Table 3A, were:
EFFEXOR: asthenia, sweating, nausea, constipation, anorexia, vomiting, somnolence, dry mouth, dizziness, nervousness, anxiety, tremor, blurred vision, and abnormal ejaculation/orgasm and impotence in men.
EFFEXOR XR: abnormal dreams, anorexia, dizziness, dry mouth, nausea, nervousness, somnolence, sweating, and tremor as well as abnormal ejaculation/orgasm in men.
During GAD trials, the most commonly observed adverse events associated with the use of
EFFEXOR XR, derived from the 2% incidence Table 4A were: nausea, dry mouth, anorexia, abnormal ejaculation, constipation, sweating, abnormal vision and impotence in men, vasodilatation, dizziness, somnolence, libido decreased, abnormal dreams, yawn and tremor.
During Social Anxiety Disorder trials, the following adverse events occurred in at least 5% of the EFFEXOR XR patients and at a rate at least twice that of the placebo group for the two placebo-controlled trials for the Social Anxiety Disorder indication (Table 5): asthenia, nausea, anorexia, insomnia, dry mouth, somnolence, dizziness, nervousness, libido decreased, anxiety, yawn, sweating, abnormal vision, as well as abnormal ejaculation and impotence in men and anorgasmia in men and women.
Adverse Events that Led to Discontinuation of Treatment in Clinical Trials
Nineteen percent (537/2897) of EFFEXOR and 12% (88/705) of EFFEXOR XR-treated patients in Phase II and III depression studies discontinued treatment due to an adverse reaction.
Approximately 18% of the 1381 patients who received EFFEXOR XR capsules for up to 8 weeks in placebo-controlled clinical trials for GAD discontinued treatment due to an adverse experience, compared with 12% of the 555 placebo-treated patients in those studies. The more common events ($ 1%) associated with discontinuation of treatment and considered to be drug-related (i.e., those events associated with dropout at a rate approximately twice or greater for venlafaxine compared to placebo) are shown in Table 2.
TABLE 2: ADVERSE REACTIONS (PERCENTAGE) LEADING TO DISCONTINUATION
OF TREATMENT
EFFEXOR Depression Indication (n=2897) | PLACEBO Depression Indication (n=609) | EFFEXOR XR Depression Indication (n=705) | PLACEBO Depression Indication (n=285) | EFFEXOR XR Anxiety Indication (n=1381) | PLACEBO Anxiety Indication (n=555) | |
CNS Somnolence Insomnia Dizziness Nervousness Anxiety Tremor | 3 3 3 2 2 <1 | 1 1 <1 <1 1 <1 | 2 <1 2 <1 <1 <1 | <1 <1 1 1 <1 <1 | 3 3 4 2 1 # 1 | <1 <1 2 <1 1 0 |
Gastrointestinal Dry Mouth Anorexia Nausea Vomiting | 2 1 6 <1 | <1 <1 1 <1 | <1 <1 4 1 | 0 <1 <1 0 | 2 <1 8 1 | <1 <1 <1 <1 |
Urogenital Abnormal Ejaculation* | 3 | 0 | <1 | <1 | <1 | 0 |
Other Headache Asthenia Sweating | 3 2 2 | 1 <1 <1 | 2 # <1 <1 | 1 1 0 | 3 3 2 | <1 <1 <1 |
* : percentages based on the number of males
# : greater than 1% but active drug rate not twice rate for placebo
Incidence in Controlled Trials
The table that follows (Table 3A) enumerates adverse events that occurred at an incidence of 2% or more, and were more frequent than in the placebo group, among venlafaxine-treated depressed patients.
EFFEXOR: patients participated in 4- to 8- week placebo-controlled trials in which doses in the range of 75 to 375 mg/day were administered.
EFFEXOR XR: patients participated in 8- to 12-week placebo-controlled trials in which doses in the range of 75 to 225 mg/day were administered.
Reported adverse events were classified using a standard COSTART-based Dictionary terminology.
The prescriber should be aware that the cited frequencies for EFFEXOR XR cannot be compared with figures obtained from other clinical investigations of EFFEXOR which involved different treatments, uses and investigators. The cited figures for EFFEXOR XR, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and non-drug factors to the side effect incidence rate in the population studied.
TABLE 3A: TREATMENT-EMERGENT ADVERSE EXPERIENCE
INCIDENCE IN PLACEBO-CONTROLLED CLINICAL TRIALS (PERCENTAGE)1 IN DEPRESSED PATIENTS
| Body System | Preferred Term | EFFEXOR (n = 1033) | Placebo (n = 609) | EFFEXOR XR (n = 357) | Placebo (n = 285) |
| Body as a whole | Headache Asthenia Infection | 25 12 6 | 24 6 5 | 26 # 8 6 # | 33 7 9 |
Chills 3 <1 <1 1
| Cardiovascular | Vasodilatation Increased blood pressure/ hypertension Tachycardia | 4 2 2 | 3 <1 <1 | 4 4 <1 | 2 1 <1 |
| Dermatological | Sweating Rash | 12 3 | 3 2 | 14 1 | 3 1 |
| Gastrointestinal | Nausea Constipation Anorexia Diarrhoea Vomiting Dyspepsia Flatulence | 37 15 11 8 6 5 3 | 11 7 2 7 2 4 2 | 31 8 8 8 # 4 7 # 4 | 12 5 4 9 2 9 3 |
| Metabolic | Weight loss | 1 | <1 | 3 | 0 |
| Nervous | Somnolence Dry mouth Dizziness Insomnia Nervousness Anxiety | 23 22 19 18 13 6 | 9 11 7 10 6 3 | 17 12 20 17 10 2 # | 8 6 9 11 5 5 |
TABLE 3A: TREATMENT-EMERGENT ADVERSE EXPERIENCE INCIDENCE IN PLACEBO-CONTROLLED CLINICAL TRIALS (PERCENTAGE)1 IN DEPRESSED PATIENTS (CONTD.)
| Body System | Preferred Term | EFFEXOR (n = 1033) | Placebo (n = 609) | EFFEXOR XR (n = 357) | Placebo (n = 285) |
Tremor Abnormal Dreams Hypertonia Paraesthesia | 5 4 3 3 | 1 3 2 2 | 5 7 1 3 | 2 2 0 1 |
Libido
decreased
2 <1 3 <1
Agitation 2 <1 3 1
Depression
Thinking
abnormal
<1
<1
<1
| Respiration | Pharyngitis Yawn | 4 3 | 4 0 | 7 3 | 6 0 |
| Special Senses | Abnormal vision Taste perversion | 6 2 | 2 <1 | 4 1 | <1 <1 |
| Urogenital system | Abnormal ejaculation/ orgasm Impotence Anorgasmia Urinary frequency Urination impaired | 122 62 <13 3 2 | <12 <1 2 <1 3 2 <1 | 162 42 33 1 <1 | <12 <1 2 <1 3 1 0 |
1 Events reported by at least 2% of patients treated with EFFEXOR®/EFFEXOR® XR are included, and are rounded to the nearest %. Events for which the EFFEXOR®/EFFEXOR® XR incidence was equal to or less than placebo included the following: abdominal pain, accidental injury, anxiety, back pain, bronchitis, diarrhea, dysmenorrhoea, dyspepsia, flu syndrome, headache, infection, pain, palpitation, rhinitis and sinusitis.
# Incidence greater than 2%, but active drug incidence less than incidence for placebo.
2 Incidence based on number of male patients (For EFFEXOR: n = 439, Placebo: n = 245; For EFFEXOR XR: n = 126, Placebo: n
= 108) 3 Incidence based on number of female patients (For EFFEXOR: n = 594, Placebo: n = 364; For EFFEXOR XR: n = 231, Placebo: n =
177)
Dose Dependency of Adverse Events
A comparison of adverse event rates in a fixed-dose study comparing EFFEXOR Tablets 75,
225, and 375 mg/day with placebo in depressed patients revealed a dose dependency for some of the more common adverse events associated with EFFEXOR use, as shown in the table that follows (Table 3B) The rule for including events was to enumerate those that occurred at an incidence of 5% or more for at least one of the venlafaxine groups and for which the incidence was at least twice the placebo incidence for at least one EFFEXOR group. Tests for potential dose relationships for these events (Cochran-Armitage Test, with a criterion of exact 2-sided p-value # 0.05) suggested a dose-dependency for several adverse events in this list, including chills, hypertension, anorexia, nausea, agitation, dizziness, somnolence, tremor, yawning, sweating, and abnormal ejaculation.
TABLE 3B: TREATMENT-EMERGENT ADVERSE EXPERIENCE INCIDENCE
(PERCENTAGE) IN A DOSE COMPARISON TRIAL IN DEPRESSED PATIENTS
| Body System/ Preferred Term | Placebo (n = 92) | EFFEXOR Tablets (mg/day) | ||
75 (n = 89) | 225 (n = 89) | 375 (n = 88) | ||
Body as a whole Abdominal pain Asthenia Chills Infection | 3.3 3.3 1.1 2.2 | 3.4 16.9 2.2 2.2 | 2.2 14.6 5.6 5.6 | 8 14.8 6.8 2.3 |
Cardiovascular Hypertension Vasodilatation | 1.1 0 | 1.1 4.5 | 2.2 5.6 | 4.5 2.3 |
Digestive System Anorexia Dyspepsia Nausea Vomiting | 2.2 2.2 14.1 1.1 | 14.6 6.7 32.6 7.9 | 13.5 6.7 38.2 3.4 | 17 4.5 58 6.8 |
TABLE 3B: TREATMENT-EMERGENT ADVERSE EXPERIENCE INCIDENCE
(PERCENTAGE) IN A DOSE COMPARISON TRIAL IN DEPRESSED PATIENTS (CONTD.)
| Body System/ Preferred Term | Placebo (n = 92) | EFFEXOR Tablets (mg/day) | ||
75 (n = 89) | 225 (n = 89) | 375 (n = 88) | ||
Nervous Agitation Anxiety Dizziness Insomnia Libido decreased Nervousness Somnolence Tremor | 0 4.3 4.3 9.8 1.1 4.3 4.3 0 | 1.1 11.2 19.1 22.5 2.2 21.3 16.9 1.1 | 2.2 4.5 22.5 20.2 1.1 13.5 18 2.2 | 4.5 2.3 23.9 13.6 5.7 12.5 26.1 10.2 |
Respiratory Yawn | 0 | 4.5 | 5.6 | 8 |
Skin and Appendages Sweating | 5.4 | 6.7 | 12.4 | 19.3 |
Special senses Abnormality of accommodation | 0 | 9.1 | 7.9 | 5.6 |
Urogenital System Abnormal ejaculation/ orgasm Impotence (Number of men) | 0.0 0.0 (n=63) | 4.5 5.8 (n=52) | 2.2 2.1 (n=48) | 12.5 3.6 (n=56) |
The tables that follow (Table 4A and 4B) enumerate adverse events that occurred at an incidence of 2% or more, and at a higher rate than the placebo group, among EFFEXOR XR-treated anxious patients.
TABLE 4A: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN PLACEBO-
CONTROLLED EFFEXOR XR NORTH AMERICAN CLINICAL TRIALS (210 US, 214 US and 218 US) IN GAD PATIENTS1,2 ( 8-28 WEEKS, DOSAGE RANGE 75-225 MG)
Body System Preferred term | EFFEXOR XR (n = 600) | Placebo (n = 328) |
Body as a whole Asthenia Accidental injury Fever Chills | 16 5 3 3 | 10 4 2 <1 |
Cardiovascular system Vasodilatation Hypertension Tachycardia | 8 4 3 | 3 3 2 |
Digestive system Nausea Dry mouth Diarrhea Anorexia Constipation Vomiting Flatulence | 46 24 16 13 12 7 3 | 18 9 13 3 6 4 2 |
Nervous system Dizziness Somnolence Insomnia Nervousness Libido decreased Abnormal dreams Tremor Hypertonia Paresthesia | 27 24 24 13 6 6 5 4 3 | 13 11 15 8 3 3 2 3 2 |
TABLE 4A: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN PLACEBO-
CONTROLLED EFFEXOR XR NORTH AMERICAN CLINICAL TRIALS (210 US, 214 US and 218 US) IN GAD PATIENTS1,2( 8-28 WEEKS, DOSAGE RANGE 75-225 MG) (CONTD.)
Body System Preferred term | EFFEXOR XR (n = 600) | Placebo (n = 328) |
Thinking abnormal Twitching Trismus Confusion | 3 3 2 2 | 2 <1 <1 <1 |
Respiratory system Yawn Cough increased | 5 4 | <1 3 |
Skin and appendages Sweating | 12 | 2 |
Special senses Abnormal vision | 8 | 1 |
Urogenital system Abnormal ejaculation/orgasm (male)3 Anorgasmia (male)3 (female)4 Urinary frequency Impotence (male)3 Urination impaired Menstrual disorder (female)4 | 15 4 5 3 4 6 2 3 | 0 <1 <1 0 2 <1 0 2 |
1 Incidence rounded to the nearest %, for events reported by at least 2% of patients treated with EFFEXOR XR, except the following events which had an incidence equal to or less than placebo: abdominal pain, agitation, anxiety, arthralgia, back pain, chest pain, depression, dyspepsia, flu syndrome, headache, infection, migraine, myalgia, neck pain, pain, palpitation, pharyngitis, rash, rhinitis, sinusitis, and tinnitus
2 < 1% indicates an incidence greater than zero but less than 1%.
3 Incidence is based on number of male patients (For EFFEXOR XR: n = 242, Placebo: n = 131) 4 Incidence is based on number of female patients (For EFFEXOR XR: n = 358, Placebo: n = 197) TABLE 4B: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN A DOSE
COMPARISON TRIAL (378 EU, 24 WEEKS) WITH GAD PATIENTS1,2
Body System Placebo Preferred term (n = 130) | --------------EFFEXOR XR------------- | |||
37.5 mg (n = 140) | 75 mg (n = 134) | 150 mg (n = 137) | ||
Body as a whole Accidental injury Asthenia Back pain Chest pain Cyst Flu syndrome Headache Infection Withdrawal syndrome | 4 9 5 2 0 6 26 4 0 | 5 11 7 5 <1 6 28 9 0 | 5 13 5 2 2 5 24 5 0 | 7 12 5 2# 0 7 25 12 2 |
Cardiovascular System Hypertension Migraine Tachycardia Vasodilation | 2 <1 0 2# | 1 4 0 4 | 2 2# 2# 2# | 5 2# 2 4 |
Digestive System Anorexia Constipation Diarrhoea Dry mouth Dyspepsia Nausea Vomiting | 2# 5 8 4 5 14 6 | 4 8 8 6 4 22 5 | 2# 13 7 13 6 34 8 | 3 15 10 17 3 42 7 |
Musculoskeletal System Arthralgia Myalgia Tenosynovitis | 4 2# <1 | 4 1 2 | 5 <1 0 | 2# 3 0 |
TABLE 4B: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN A DOSE
COMPARISON TRIAL (378 EU, 24 WEEKS) WITH GAD PATIENTS1,2
(CONTD.)
Body System Placebo Preferred term (n = 130) | --------------EFFEXOR XR------------- | |||
37.5 mg (n = 140) | 75 mg (n = 134) | 150 mg (n = 137) | ||
Nervous System Abnormal dreams Anxiety Depersonalization Depression Dizziness Hypertonia Insomnia Libido decreased Nervousness Paresthesia Somnolence Thinking abnormal Tremor Vertigo | 2# 6 <1 2# 14 <1 10 <1 2# 2 4 0 0 <1 | 4 5 <1 4 15 3 7 3 4 1 1 2 2 2 | 6 2# <1 2 22 2# 12 2# 3 2 6 0 4 2 | 3 7 2 <1 31 3 15 4 3 10 7 0 4 0 |
Respiratory System
Bronchitis <1 3 2# 4
Cough increased 2# 3 3 2
Dyspnea 2# 1 2 0
Rhinitis 2# 4 4 3
Sinusitis <1 4 5 4
Yawn 0 0 2 5
Skin and Appendages Eczema Rash Sweating | <1 2# 5 | 2 <1 9 | 2# 3 11 | 2# 2 18 |
Special Senses Abnormal vision Conjunctivitis Mydriasis Tinnitus | 2# 0 0 <1 | <1 4 <1 4 | 8 2# <1 4 | 4 2# 2 3 |
TABLE 4B: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN A
DOSE COMPARISON TRIAL (378 EU, 24 WEEKS) WITH GAD PATIENTS1,2 (CONTD.)
Body System Placebo Preferred term (n = 130) | --------------EFFEXOR XR------------- | |||
37.5 mg (n = 140) | 75 mg (n = 134) | 150 mg (n = 137) | ||
Urogenital System Abnormal ejaculation/orgasm (male)3 Anorgasmia (male)3 female)4 Dysmenorrhoea (female)4 Dysuria Impotence (male)3 Menorrhagia (female)4 Urinary frequency | 0 0 0 3 0 0 0 2# | 1 2 0 4 <1 2 3 2 | 0 0 0 1 2 2 1 <1 | 2 8 2 1 2# 3 2 2# |
1 Incidence rounded to the nearest %, for events reported by at least 2% of patients in any EFFEXOR XR treatment group and at a incidence greater than the respective placebo incidence # indicates that the incidence is less than 2% but rounds to 2%.
2 < 1% indicates an incidence greater than zero but less than 1%.
3 Incidence is based on number of male patients (For EFFEXOR XR: n = 60 (37.5 mg), 51 (75 mg), 48 (150 mg);
Placebo: n = 54)
4 Incidence is based on number of female patients (For EFFEXOR XR: n = 80 (37.5 mg), 83 (75 mg), 89 (150 mg); Placebo: n = 76)
The table that follows (Table 5) enumerates adverse events that occurred at an incidence of 2% or more, and were more frequent than in the placebo group, among venlafaxine-treated patients with Social Anxiety Disorder.
TABLE 5: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN
SHORT-TERM, PLACEBO-CONTROLLED EFFEXOR XR CLINICAL TRIALS (387 EU/CA and 393 US) IN SOCIAL ANXIETY DISORDER PATIENTS1,2 (12 WEEKS, DOSAGE RANGE 75-225 MG)
Body System Preferred term | EFFEXOR XR (n = 277) | Placebo (n = 274) |
Body as a Whole Headache Asthenia Flu syndrome Accidental injury Abdominal pain | 34 17 6 5 4 | 33 8 5 3 3 |
Cardiovascular System Hypertension Vasodilatation Palpitation | 5 3 3 | 4 1 1 |
Digestive System Nausea Anorexia Constipation Diarrhea Vomiting Eructation | 29 20 8 6 3 2 | 9 1 4 5 2# 0 |
Metabolic and Nutritional Weight loss | 4 | 0 |
Nervous System Insomnia Dry mouth Dizziness Somnolence Nervousness Libido decreased Anxiety Agitation | 23 17 16 16 11 9 5 4 | 7 4 8 8 3 <1 3 1 |
TABLE 5: TREATMENT-EMERGENT ADVERSE EVENT INCIDENCE (%) IN
SHORT-TERM, PLACEBO-CONTROLLED EFFEXOR XR CLINICAL
TRIALS (387 EU/CA and 393 US) IN SOCIAL ANXIETY DISORDER
PATIENTS1,2 (12 WEEKS, DOSAGE RANGE 75-225 MG) (CONTD)
Body System Preferred term | EFFEXOR XR (n = 277) | Placebo (n = 274) |
Tremor Abnormal dreams Paresthesia Twitching | 4 4 3 2 | <1 <1 <1 0 |
Respiratory System Yawn Sinusitis | 5 2 | <1 1 |
Skin Sweating | 13 | 2# |
Special Senses Abnormal vision | 6 | 3 |
Urogenital System Abnormal ejaculation/orgasm (men)3 (women)4 Impotence3 Anorgasmia (men)3 (women)4 | 12 3 10 5 6 | <1 0 1 <1 0 |
1 Incidence rounded to the nearest %, for events reported by at least 2% of patients in any EFFEXOR XR treatment group, except for the following events for which the EFFEXOR XR reporting rate was less than or equal to the placebo rate: back pain, depression, dysmenorrhea, dyspepsia, infection, myalgia, pain, pharyngitis, rash, rhinitis, and upper respiratory infection. # indicates that the incidence is less than 2% but rounds to 2% 2 <1% means greater than zero but less than 1%. 3 Percentage based on the number of males (EFFEXOR XR = 158, placebo = 153). 4 Percentage based on the number of females (EFFEXOR XR = 119, placebo = 121). | ||
The Treatment-Emergent Adverse Event Incidence profile of EFFEXOR XR in a 28-week study (390 EU) was similar to that observed in the above two 12-week studies.
Adaptation to Certain Adverse Events
In premarketing experience with EFFEXOR Tablets over a 6-week period, and EFFEXOR XR capsules over a 12 week period, there was evidence of adaptation to some adverse events with continued therapy (e.g., dizziness and nausea), but less to other effects (e.g., abnormal ejaculation and dry mouth). The incidence of nausea in the GAD studies, during weeks 1 and 2 were 28% and 14% for EFFEXOR XR- treated patients and 6% and 4% for placebo-treated patients, respectively. The incidence of dizziness during weeks 1 and 2 were 12% and 6% for
EFFEXOR XR-treated patients and 4% and 4% for placebo-treated patients, respectively.
Discontinuation Symptoms
Abrupt discontinuation, dose reduction, or tapering of venlafaxine at various doses has been found to be associated with the appearance of new symptoms, the frequency of which increased with increased dose level and with longer duration of treatment. Symptoms associated with discontinuation include but are not limited to: anorexia, anxiety, agitation, confusion, convulsions, coordination impaired, diarrhea, dizziness, dry mouth, dysphoric mood, fasciculation, fatigue, headache, hypomania, insomnia, nausea, nervousness, nightmares, paresthesia, electric shock sensations, sensory disturbances (including shock like electrical sensations), sleep disturbances, somnolence, sweating, tinnitus, vertigo, and vomiting.
Patients should be monitored for these or any other symptoms when discontinuing treatment, regardless of the indication for which EFFEXOR is being prescribed. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, dose titration should be managed on the basis of the patient’s clinical response (See “PRECAUTIONS” and
“DOSAGE AND ADMINISTRATION” sections for details).
Vital Sign Changes
Treatment with EFFEXOR Tablets (averaged over all dose groups) in clinical trials was associated with a mean increase in pulse rate of approximately 3 beats per minute, compared to no change for placebo. It was associated with mean increases in diastolic blood pressure ranging from 0.7 to 2.5 mm Hg averaged over all dose groups, compared to mean decreases ranging from
0.9 to 3.8 mm Hg for placebo. However, there is a dose dependency for blood pressure increase
(see the “Sustained Hypertension” section of WARNINGS for effects on blood pressure).
Treatment with EFFEXOR XR Capsules for up to 12 weeks in premarketing depression trials was associated with a mean increase in pulse rate of approximately 2 beats per minute, compared with 1 beat per minute for placebo. It was associated with mean increases in diastolic blood pressure ranging from 0.7 to 0.9 mm Hg, compared with mean decreases ranging from 0.5 to 1.4 mm Hg for placebo (see WARNINGS). EFFEXOR XR treatment for up to 6 months in premarketing placebo-controlled GAD trials was associated with a mean final on-therapy increase in pulse rate of approximately 2 beats per minute, compared with less than 1 beat per minute for placebo.
EFFEXOR XR treatment for up to 12 weeks in premarketing placebo-controlled Social Anxiety
Disorder trials was associated with mean final on-therapy increase in pulse rate of approximately
5 beats per minute, compared with no change for placebo.
Laboratory Changes - Cholesterol
Clinically and statistically relevant increases in cholesterol levels have been noted in studies using EFFEXOR Tablets and EFFEXOR XR Capsules (see PRECAUTIONS-Serum
Cholesterol Elevation).
EFFEXOR Tablets:
Patients treated with EFFEXOR tablets for at least 3 months in placebo-controlled 12-month extension trials for Major Depressive Disorders had a mean final on-therapy increase in total cholesterol of 9.1 mg/dL (0.2364 mmol/L). compared with a decrease of 7.1 mg/dL (0.1835 mmol/L) among placebo-treated patients. This increase was duration dependent over the study period and tended to be greater with higher doses. Clinically relevant increases in serum cholesterol, defined as 1) a final on-therapy increase in serum cholesterol $50 mg/dL (1.2930 mmol/L) from baseline and to a value $261 mg/dL (6.7495 mmol/L) or 2) an average on-therapy increase in serum cholesterol $50 mg/dL (1.2930 mmol/L) from baseline and to a value $261 mg/dL (6.7495 mmol/L), were recorded in 5.3% of venlafaxine-treated patients and 0.0% of placebo-treated patients.
EFFEXOR XR Capsules:
EFFEXOR XR (venlafaxine hydrochloride) extended-release capsules treatment for up to 12 weeks in premarketing placebo-controlled trials for major depressive disorder was associated with a mean final on-therapy increase in serum cholesterol concentration of approximately 1.5 mg/dL (0.0381 mmol/L) compared with a mean final decrease of 7.4 mg/dL (0.1919 mmol/L) for placebo.
EFFEXOR XR treatment for up to 8 weeks and up to 6 months in premarketing placebo-controlled GAD trials was associated with mean final on-therapy increases in serum cholesterol concentration of approximately 1.0 mg/dL (0.0247 mmol/L) and 2.3 mg/dL (0.0606 mmol/L), respectively while placebo subjects experienced mean final decreases of 4.9 mg/dL (0.1278 mmol/L) and 7.7 (0.1990 mmol/L) mg/dL, respectively.
Elevations of total serum cholesterol, High Density Lipoprotein Cholesterol (HDL), Low
Density Lipoprotein Cholesterol (LDL) and the overall ratio of Total Cholesterol/HDL have been observed in placebo controlled clinical trials for Social Anxiety Disorder (SAD).
Measurement of serum cholesterol levels (including a complete lipid profile/fractionation and an assessment of the patient’s individual risk factors) should be considered especially during long-term treatment.
Patients treated with EFFEXOR XR for up to 12 weeks in premarketing placebo-controlled Social Anxiety Disorder trials had a mean final on-therapy increases in total serum cholesterol concentration of approximately 11.4 mg/dL (0.295 mmol/L), increases in HDL cholesterol of 2.7 mg/dL (0.069 mmol/L), and increases in LDL cholesterol of 8.2 mg/dL (0.212 mmol/L).
ECG Changes
In an analysis of ECGs obtained in 769 patients treated with EFFEXOR Tablets and 450 patients treated with placebo in controlled clinical trials in depression, the only statistically significant difference observed was for heart rate, i.e., a mean increase from baseline of 4 beats per minute for EFFEXOR.
An analysis of ECGs obtained in 357 patients treated with EFFEXOR XR and 285 patients treated with placebo in controlled clinical trials in depression and the electrocardiograms for 815 patients who received EFFEXOR XR and 379 patients who received placebo for up to 6 months in double-blind, placebo-controlled trials in anxiety were analyzed. The mean change from baseline in corrected QT interval (QTc) for EFFEXOR XR-treated patients was increased relative to that for placebo-treated patients in the clinical trials for depression (see
PRECAUTIONS).
In North American clinical trials for Generalized Anxiety Disorder, mean reductions in PR interval (3-6 msec decrease) were reported during EFFEXOR XR treatment which represented statistically significant differences from the corresponding placebo groups (1-3 msec increase).
The clinical significance of these changes is not definitively known.
Other Events Observed During the Premarketing Evaluation of Venlafaxine
During the premarketing assessment of EFFEXOR tablets, multiple doses were administered to
2897 patients in phase II-III depression studies. Multiple doses of EFFEXOR XR were administered to 705 patients in phase III depression studies (as well as 96 patients on
EFFEXOR Tablets), to 1381 patients in phase III GAD studies and 277 patients in phase III
Social Anxiety Disorder studies. The conditions and duration of exposure to venlafaxine in both development programs varied greatly, and included (in overlapping categories) open and double-blind studies, uncontrolled and controlled studies, inpatient (EFFEXOR® Tablets only)
and outpatient studies, fixed-dose and titration studies. Untoward events associated with this exposure were recorded by clinical investigators using terminology of their own choosing.
Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse events without first grouping similar types of untoward events into a smaller number of standardized event categories.
In the tabulations that follow, reported adverse events were classified using a standard
COSTART-based Dictionary terminology. The frequencies presented, therefore, represent the proportion of the 5,356 patients exposed to multiple doses of either formulation of venlafaxine who experienced an event of the type cited on at least one occasion while receiving venlafaxine.
All reported events are included except those already listed in Tables 3A, 3B, 4A, 4B and 5, and those events for which a drug cause was remote. If the COSTART term for an event was so general as to be uninformative, it was replaced with a more informative term. It is important to emphasize that, although the events reported occurred during treatment with venlafaxine, they were not necessarily caused by it.
Events are further categorized by body system and listed in order of decreasing frequency according to the following definitions: frequent adverse events are those occurring on one or more occasions in at least 1/100 patients; infrequent adverse events are those occurring in 1/100 to 1/1000 patients; rare adverse events are those occurring in fewer than 1/1000 patients.
Body as a whole :Infrequent: face edema, intentional injury, malaise, moniliasis, neck rigidity, overdose, pelvic pain, photosensitivity reaction, suicide attempt, withdrawal syndrome.
Rare: appendicitis, bacteremia, carcinoma, cellulitis, anaphylaxis.
Cardiovascular system:
Frequent: postural hypotension.
Infrequent: angina pectoris, arrhythmia, extra systoles, hypotension, peripheral vascular disorder (mainly cold feet and/or cold hands), syncope, thrombophlebitis.
Rare: aortic aneurysm, arteritis, first degree atrioventricular block, bigeminy, bundle branch block, bradycardia, capillary fragility, cardiovascular disorder (includes mitral valve and circulatory disturbances), cerebral ischemia, coronary artery disease, heart arrest, heart failure, mucocutaneous hemorrhage, myocardial infarct, pallor.
Digestive system:
Frequent: eructation, increased appetite.
Infrequent: bruxism, colitis, dysphagia, tongue edema, esophagitis, gastritis, gastroenteritis, gastrointestinal ulcer, gingivitis, glossitis, rectal hemorrhage, hemorrhoids, melena, oral moniliasis, stomatitis, mouth ulceration.
Rare: cheilitis, cholecystitis, cholelithiasis, esophageal spasms, hematemesis, gastrointestinal hemorrhage, gum hemorrhage, hepatitis, ileitis, jaundice, intestinal obstruction, parotitis, periodontitis, proctitis, increased salivation, soft stools, tongue discoloration.
Endocrine system:
Rare: goiter, hyperthyroidism, hypothyroidism, thyroid nodule, thyroiditis.
Hemic and lymphatic system:
Frequent: ecchymosis.
Infrequent: anemia, leukocytosis, leukopenia, lymphadenopathy, thrombocythemia, thrombocytopenia, mucous membrane bleeding.
Rare: basophilia, bleeding time increased, cyanosis, eosinophilia, lymphocytosis, multiple myeloma, purpura.
Metabolic and nutritional:
Frequent: edema, weight gain, serum cholesterol increase.
Infrequent: alkaline phosphatase increased, dehydration, hypercholesterolemia, hyperglycemia, hyperlipemia, hypokalemia, hyponatremia, SGOT (AST) increased, SGPT (ALT) increased, thirst, SIADH.
Rare: alcohol intolerance, bilirubinemia, BUN increased, creatinine increased, diabetes mellitis, dehydration, glycosuria, gout, hemochromatosis, hypercalcinuria, hyperkalemia,
hyperphosphatemia, hyperuricemia, hypoglycemia, hypophosphatemia, hypoproteinemia, uremia.
Musculoskeletal system:
Infrequent: arthritis, arthrosis, bone pain, bone spurs, bursitis, leg cramps, myasthenia, tenosynovitis.
Rare: pathological fracture, myopathy, osteoporosis, osteosclerosis, plantar fasciitis, rheumatoid arthritis, tendon rupture.
Nervous system:
Frequent: amnesia, confusion, depersonalization, emotional lability, hypesthesia, trismus, vertigo.
Infrequent: akathisia, apathy, ataxia, convulsion, CNS stimulation, euphoria, hallucinations, hostility, hyperesthesia, hyperkinesia, hypotonia, incoordination, manic reaction, myoclonus, neuralgia, neuropathy, psychosis, serotonergic syndrome, seizure, abnormal speech, stupor.
Rare: akathisia, akinesia, alcohol abuse, aphasia, bradykinesia, buccoglossal syndrome, cerebrovascular accident, feeling drunk, loss of consciousness, delusions, dementia, dystonia, facial paralysis, abnormal gait, Guillain-Barré Syndrome, hyperchlorhydria, impulse control difficulties, hypokinesia, libido increased, neuritis, nystagmus, paranoid reaction, paresis, psychotic depression, reflexes decreased, reflexes increased, suicidal ideation, torticollis.
Respiratory system:
Frequent: dyspnea.
Infrequent: asthma, chest congestion, epistaxis, hyperventilation, laryngismus, laryngitis, pneumonia, voice alteration.
Rare: atelectasis, hemoptysis, hypoventilation, hypoxia, larynx edema, pleurisy, pulmonary embolus, sleep apnea, sputum increased.
Skin and appendages:
Frequent: pruritus.
Infrequent: acne, alopecia, brittle nails, contact dermatitis, dry skin, eczema, skin hypertrophy, maculopapular rash, psoriasis, urticaria.
Rare: erythema nodosum, exfoliative dermatitis, lichenoid dermatitis, hair discoloration, skin discoloration, furunculosis, hirsutism, leukoderma, petechial rash, pustular rash, vesiculobullous rash, seborrhea, skin atrophy, skin striae.
Special senses:
Frequent: abnormality of accommodation, abnormal vision, mydriasis, taste perversion.
Infrequent: cataract, conjunctivitis, corneal lesion, diplopia, dry eyes, eye pain, hyperacusis, otitis media, parosmia, photophobia, taste loss, visual field defect.
Rare: blepharitis, chromatopsia, conjunctival edema, deafness, exophthalmos, glaucoma, retinal hemorrhage, subconjunctival hemorrhage, keratitis, labyrinthitis, miosis, papilledema, decreased pupillary reflex, otitis externa, scleritis, uveitis, vitreous disorder.
Urogenital system:
Frequent: anorgasmia - female*, dysuria, erectile dysfunction*, metrorrhagia*, prostatic disorder (includes prostatitis and enlarged prostate)*, vaginitis*.
Infrequent: albuminuria, amenorrhea*, cystitis, dysuria, hematurea, leukorrhea*, menorrhagia*, nocturia, abnormal orgasm - female*, bladder pain, breast pain, polyuria, pyuria, urinary incontinence, urinary retention, urinary urgency, vaginal hemorrhage*.
Rare: abortion*, anuria, breast discharge, breast engorgement, breast enlargement, endometriosis, fibrocystic breast*, calcium crystalluria, cervicitis*, ovarian cyst*, prolonged erection*, female lactation*, gynecomastia*, hypomenorrhea*, kidney calculus, kidney pain, kidney function abnormal, mastitis*, menopause,* oliguria, orchitis, pyelonephritis, salpingitis*, urolithiasis, uterine hemorrhage*, uterine spasm*.
* Based on the number of men and women, as appropriate.
Postmarketing Experience
Voluntary reports of other adverse events temporally associated with the use of EFFEXOR® that have been received since market introduction and that may have no causal relationship with the use of EFFEXOR® include the following:
Body as a whole: anaphylaxis, congenital anomalies, neuroleptic malignant syndrome-like events (including the case of a 10-year old boy who may have been taking methylphenidate, was treated and recovered), serotonin syndrome
Cardiovascular system: congestive heart failure, deep vein thrombosis, EKG abnormalities (such as atrial fibrillation, bigeminy, supraventricular tachycardia, ventricular extrasystole, ventricular tachycardia), heart arrest, hemorrhage, myocardial infarction, torsades de pointes
Digestive system: bruxism, gastrointestinal bleeding, hepatic events (including GGT elevation;
abnormalities of unspecified liver function tests; liver damage, necrosis or failure; and fatty liver), pancreatitis, diarrhoea
Endocrine system: prolactin increased
Hemic and lymphatic system: agranulocytosis, aplastic anemia, neutropenia, pancytopenia
Metabolic and Nutritional: CPK increased, dehydration, LDH increased, hepatitis, syndrome of inappropriate antidiuretic hormone secretion, weight loss
Musculoskeletal: Rhabdomyolysis
Nervous system: agitation, abnormal gait, catatonia, delirium, extrapyramidal symptoms
(including dystonia, dyskinesia, tardive dyskinesia), grand mal seizures, increased muscle tonus, involuntary movements, panic, paresthesia, neuroleptic malignant syndrome, sedation, shock-like electrical sensations (in some cases, subsequent to the discontinuation of EFFEXOR or tapering of dose)
Respiratory system: Pulmonary eosinophilia
Skin and appendages: epidermal necrosis/Stevens-Johnson syndrome, erythema multiform, sweating including night sweats
Special senses: eye hemorrhage, tinnitus
Urogenital system: renal failure
SYMPTOMS AND TREATMENT OF OVERDOSAGE
EFFEXOR Tablets
There were 14 reports of acute overdose with EFFEXOR (venlafaxine HCl), either alone or in combination with other drugs and/or alcohol, among the patients included in the premarketing evaluation. The majority of the reports involved ingestions in which the total dose of EFFEXOR taken was estimated to be no more than several-fold higher than the usual therapeutic dose. The
3 patients who took the highest doses were estimated to have ingested approximately 6.75 g,
2.75 g and 2.5 g. The resultant peak plasma levels of venlafaxine for the latter 2 patients were
6.24 and 2.35 :g/mL, respectively, and the peak plasma levels of O-desmethylvenlafaxine were
3.37 and 1.30 :g/mL, respectively. Plasma venlafaxine levels were not obtained for the patient who ingested 6.75 g of venlafaxine. All 14 patients recovered without sequelae. Most patients reported no symptoms. Among the remaining patients, somnolence was the most commonly reported symptom. The patient who ingested 2.75 g of venlafaxine was observed to have 2 generalized convulsions and a prolongation of QTc to 500 msec, compared with 405 msec at baseline. Mild sinus tachycardia was reported in 2 of the other patients.
EFFEXOR XR Capsules
Among the patients included in the premarketing evaluation of venlafaxine extended release capsules, there were 2 reports of acute overdosage with EFFEXOR XR in depression trials, either alone or in combination with other drugs. One patient took a combination of 6 g of
EFFEXOR® XR and 2.5 mg of lorazepam. This patient was hospitalized, treated
symptomatically, and recovered without any untoward effects. The other patient took 2.85 g of
EFFEXOR XR. This patient reported paresthesia of all four limbs but recovered without sequelae. There were 2 reports of acute overdose with EFFEXOR XR in anxiety trials. One patient took a combination of 0.75 g EFFEXOR XR and 200 mg of paroxetine and 50 mg of zolpidem. This patient was described as being alert, able to communicate, and a little sleepy.
This patient was hospitalized, treated with activated charcoal, and recovered without any untoward effects. The other patient took 1.2 g of EFFEXOR XR. This patient recovered and no other specific problems were found. The patient had moderate dizziness, nausea, numb hands and feet, and hot-cold spells 5 days after the overdose. There were no reports of acute overdose with EFFEXOR XR in Social Anxiety Disorder trials.
In postmarketing experience, electrocardiogram changes (e.g., QT prolonged, bundle branch block, QRS prolonged), sinus and ventricular tachycardia, bradycardia, vertigo, hypotension, decreased levels of consciousness (ranging from somnolence to coma) and seizures have been reported in association with overdose of EFFEXOR, either alone or in combination with other drugs and/or alcohol. In postmarketing experience there have been reports of fatalities in patients taking overdoses of EFFEXOR, predominantly in combination with alcohol and/or other drugs.
Overdosage Management
Treatment should consist of those general measures employed in the management of overdosage with any antidepressant. Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm and vital signs. General supportive and symptomatic measures are also recommended. Induction of emesis is not recommended. Gastric lavage with a large bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion or in symptomatic patients. Activated charcoal should be administered.
Due to the large volume of distribution of this drug, forced diuresis, dialysis, hemoperfusion and exchange transfusion are unlikely to be of benefit. No specific antidotes for venlafaxine are known.
In managing overdosage, consider the possibility of multiple drug involvement. The physician should consider contacting a poison control centre for information on the treatment of any overdose.
DOSAGE AND ADMINISTRATION
EFFEXOR and EFFEXOR XR (venlafaxine) are not indicated for use in children under 18 years of age (see WARNINGS: POTENTIAL ASSOCIATION WITH BEHAVIOURAL
AND EMOTIONAL CHANGES, INCLUDING SELF-HARM).
ADULTS:
Patients with Major Depressive Disorder
EFFEXOR Tablets
The recommended treatment dose is 75 mg per day, administered in two or three divided doses, taken with food. For some patients, it may be desirable to start at 37.5 mg/day for 4-7 days to allow new patients to adjust to the medication before increasing to 75 mg/day. If the expected clinical improvement does not occur after a few weeks, a gradual dose increase to 150 mg/day may be considered. If needed, the dose may be further increased up to 225 mg/day. Increments of up to 75 mg/day should be made at intervals of no less than 4 days. In outpatient settings there was no evidence of the usefulness of doses greater than 225 mg/day for moderately depressed patients. More severely depressed inpatients have responded to higher doses, between
350 and 375 mg/day, given in three divided doses. The maximum dose recommended is 375 mg per day (in an inpatient setting).
EFFEXOR XR Capsules
The recommended dose for EFFEXOR XR is 75 mg/day, administered once daily with food, either in the morning or in the evening. For some patients, it may be desirable to start at 37.5 mg/day for 4-7 days to allow new patients to adjust to the medication before increasing to 75 mg/day. Each capsule should be swallowed whole with water. It should not be divided, crushed, chewed, or placed in water. While the relationship between dose and antidepressant response for
EFFEXOR XR has not been adequately explored patients not responding to the initial 75 mg may benefit from dose increases. Depending on tolerability and the need for further clinical effect, the dose should be increased by up to 75 mg/day up to a maximum of 225 mg/day as a single dose for moderately depressed outpatients. Dose increments should be made at intervals of approximately 2 weeks or more, but not less than 4 days. There is very limited experience with EFFEXOR XR at doses higher than 225 mg/day, or in severely depressed inpatients.
It should be noted that, while the maximum recommended dose for moderately depressed outpatients is also 225 mg/day for EFFEXOR Tablets, more severely depressed inpatients responded to a mean dose of 350 mg/day (range of 150 to 375 mg/day).
Maintenance Treatment: Major Depressive Disorder
There is no body of evidence available to answer the question of how long a patient should continue to be treated with EFFEXOR Tablets or EFFEXOR XR Capsules.
It is generally agreed that acute episodes of depression require several months or longer of sustained pharmacological therapy beyond response to the acute episode.
Maintenance of efficacy of EFFEXOR XR has been shown in a placebo controlled study in which patients responding during 8 weeks of acute treatment with EFFEXOR XR were assigned randomly to placebo or to the same dose of EFFEXOR XR (75, 150, or 225 mg/day, in the morning (i.e. qAM) during 26 weeks of maintenance treatment (see CLINICAL TRIALS).
A second longer-term study has demonstrated the efficacy of EFFEXOR Tablets (100 to 200 mg/day, on a b.i.d. schedule) in maintaining an antidepressant response in patients with recurrent depression who had responded during an initial 26 weeks of treatment and were then randomly assigned to placebo or EFFEXOR Tablets for periods of up to 52 weeks on the same dose (see
CLINICAL TRIALS).
It is not known whether or not the dose of EFFEXOR/EFFEXOR XR needed for maintenance treatment is identical to the dose needed to achieve an initial response. Patients should be periodically reassessed to determine the need for maintenance treatment and the appropriate dose for such treatment.
Patients with GAD
The recommended starting dose of EFFEXOR XR is 37.5 mg/day administered as a single dose, taken with food, for 4-7 days. The usual dose is 75 mg/day administered as a single dose.
Subsequent dosage increments of up to 75 mg/day may be considered, if clinically warranted.
Dose increments should be made as needed at intervals of not less than 4 days. The maximum recommended daily dose is 225 mg/day as a single dose.
Patients with Social Anxiety Disorder (Social Phobia)
For most patients, the recommended starting dose for EFFEXOR XR is 75 mg/day, administered in a single dose. For some patients, it may be desirable to start at 37.5 mg/day for 4 to 7 days, to allow new patients to adjust to the medication before increasing to 75 mg/day. Dose increases should be in increments of up to 75 mg/day, as needed, up to a maximum of 225 mg/day. Dose increments should be made at intervals of not less than 4 days.
Switching Patients from EFFEXOR Tablets:
Depressed patients who are currently being treated at a therapeutic dose with EFFEXOR may be switched to EFFEXOR® XR at the nearest equivalent dose (mg/day), e.g., 37.5 mg EFFEXOR two-times-a-day to 75 mg EFFEXOR XR once daily. However, individual dosage adjustments may be necessary.
Patients With Hepatic Impairment:
Given the decrease in clearance and increase in elimination half-life for both venlafaxine and
ODV that is observed in patients with hepatic cirrhosis compared with normal subjects (see
CLINICAL PHARMACOLOGY), the total daily dose must be reduced by about 50% in patients with moderate hepatic impairment. For such patients, it may be desirable to start at 37.5 mg/day. Since there was much individual variability in clearance between patients with cirrhosis, it may be necessary to reduce the dose by even more than 50%, and individualization of dosing may be desirable in some patients.
Patients with Renal Impairment
Given the decrease in clearance for venlafaxine and increase in elimination half-life for both venlafaxine and ODV that is observed in patients with renal impairment (GFR = 10-70 mL/min)
compared to normal subjects (see CLINICAL PHARMACOLOGY), the total daily dose must be decreased by 25%-50%. In patients undergoing hemodialysis, the total daily dose must be reduced by 50% and the dose be withheld until the dialysis treatment is completed (4 hrs). For such patients, it may be desirable to start at 37.5 mg/day. Since there is so much individual variability in clearance among patients with renal impairment, individualization of dosing may be desirable.
Treatment of Pregnant Women During the Third Trimester
Post-marketing reports indicate that some neonates exposed to EFFEXOR or EFFEXOR XR,
SSRIs (Selective Serotonin Reuptake Inhibitors), or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. (see PRECAUTIONS). When treating a pregnant woman with EFFEXOR or
EFFEXOR XR during the third trimester, the physician should carefully consider the potential risks and benefits of treatment..
Elderly Patients
No dose adjustment is recommended for elderly patients solely on the basis of their age. As with any antidepressant or anxiolytic, or drug for treatment of Social Anxiety Disorder, however, caution should be exercised in treating the elderly. When individualizing the dosage, extra care should be taken when increasing the dose.
Children
See WARNINGS: POTENTIAL ASSOCIATION WITH BEHAVIOURAL AND
EMOTIONAL CHANGES, INCLUDING SELF-HARM.
Maintenance/Continuation/Extended Treatment
There is no body of evidence available to answer the question of how long a patient should continue to be treated with venlafaxine for depression, GAD or Social Anxiety Disorder. It is generally agreed that acute episodes of major depression require several months or longer of sustained pharmacotherapy. Whether the dose needed to induce remission is identical to the dose needed for maintenance is unknown.
In patients with Social Anxiety Disorder, there are no efficacy data beyond 12 weeks of treatment with EFFEXOR XR. The need for continuing medication in patients with Social
Anxiety Disorder who improve with EFFEXOR XR treatment should be periodically reassessed.
Discontinuing Venlafaxine
When discontinuing venlafaxine after more than 1 week of therapy, it is generally recommended that the dose be tapered gradually to minimize the risk of discontinuation symptoms. Discontinuation symptoms have been assessed both in patients with depression and in those with GAD. Abrupt discontinuation, dose reduction, or tapering of venlafaxine at various doses has been found to be associated with the appearance of new symptoms, the frequency of which increased with higher dose levels and with longer duration of treatment.
Reported symptoms include but are not limited to the following: anorexia, anxiety, agitation, confusion, convulsions, coordination impaired, diarrhea, dizziness, dry mouth, dysphoric mood, fasciculation, fatigue, headache, hypomania, insomnia, nausea, nervousness, nightmares, paresthesia, electric shock sensations, sensory disturbances (including shock like electrical sensations), sleep disturbances, somnolence, sweating, tinnitus, vertigo, and vomiting. Where such symptoms occurred they were usually self-limiting but in a few patients continued for several weeks. It is therefore recommended that the dosage of EFFEXOR and EFFEXOR XR be tapered gradually and the patient monitored. The period required for tapering may depend on the dose, duration of therapy and the individual patient. If venlafaxine has been used for more than 6 weeks, tapering over at least a two week period is recommended.
Switching Patients to or from a Monoamine Oxidase Inhibitor:
At least 14 days should elapse between discontinuation of an MAOI and initiation of therapy with EFFEXOR/EFFEXOR XR. In addition, at least 14 days should be allowed after stopping
EFFEXOR /EFFEXOR XR before starting an MAOI (see "CONTRAINDICATIONS").
PHARMACEUTICAL INFORMATION
Drug Substance:
Proper Name: Venlafaxine Hydrochloride
Chemical Name: (R/S)-1-[2-(dimethylamino)-1-(4-methoxyphenyl) ethyl]
cyclohexanol hydrochloride;
or
(±)-1-["[(dimethylamino)methyl]-p-methoxy-benzyl]
cyclohexanol hydrochloride.
Structural Formula: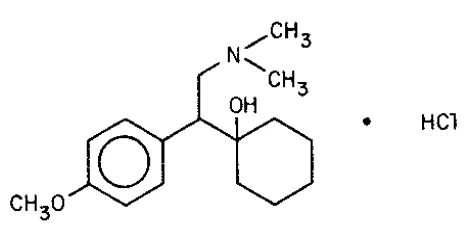
Molecular Weight: 313.87
Physical Form: White to off-white crystalline solid Solubility:
Water: 540, 542, 501 and 21.6 mg/mL at pH 1.0, 5.38, 7.09 and 7.97
Ethanol: 91.7 mg/mL
Propylene Glycol: 200 mg/mL
Glycerin: 115 mg/mL
pKa value: 9.4
Composition:
EFFEXOR® Tablets
Medicinal Ingredients Non-medicinal Ingredients
Venlafaxine Hydrochloride Microcrystalline cellulose, NF
Lactose, NF Hydrous
Cosmetic Brown Iron Oxide
Ferric Oxide, NF Yellow
Sodium Starch Glycolate, NF
Magnesium Stearate, NF
Stability and Storage Recommendations
Store at room temperature (15-30°C), in a dry place. EFFEXOR® XR Capsules (extended release)
Medicinal Ingredients Non-medicinal Ingredients:
Venlafaxine Hydrochloride Ethylcellulose, NF
Gelatin, NF
Hydroxypropyl methylcellulose, USP
Iron Oxide, NF
Microcrystalline Cellulose, NF
Titanium Dioxide, USP
White Tek SB-0007 and/or Opacode Red S-1-15034 ink
Talc, USP
EFFEXOR® XR Capsules, the extended release formulation of venlafaxine, contains spheroids which release the drug slowly into the digestive tract. The insoluble portion of these spheroids is eliminated and may be seen in the stools.
Stability and Storage Recommendations
Store at room temperature (15-30°C), in a dry place.
AVAILABILITY OF DOSAGE FORMS
PrEFFEXOR (venlafaxine HCl) Tablets are available, in bottles of 100 tablets, in the following tablet strengths (potency is expressed in terms of venlafaxine base): 12.5 mg Oval, peach-coloured compressed tablet with “W” on one side and “12.5” on the other side.
25 mg Shield-shaped, peach-coloured compressed tablet, with a score, with “W” on one side and “25” on the other side.
37.5 mg Shield-shaped, peach-coloured compressed tablet, with a score, with “W” on one side and “37.5” on the other side.
50 mg Shield-shaped, peach-coloured compressed tablet, with a
score, with “W” on one side and “50” on the other side.
75 mg Shield-shaped, peach-coloured compressed tablet, with a score, with “W” on one side and “75” on the other side.
100 mg Shield-shaped, peach-coloured compressed tablet, with a score, with “W” on one side and “100” on the other side.
PrEFFEXOR XR (venlafaxine HCl) extended-release capsules are available in bottles of 100 capsules and 500 capsules, in the following dosage strengths (potency is expressed in terms of venlafaxine base):
37.5 mg Hard gelatin capsule with gray cap and peach body, with “W” and “Effexor XR”
on the cap and “37.5" on the body, in red ink.
75 mg Hard gelatin capsule with peach cap and body, with “W” and “Effexor XR” on the cap and “75" on the body, in red ink.
100 mg Hard gelatin capsule with dark orange cap and peach body, with “W” and