


Product Monograph - Famotidine (Acid Controller) Tablets
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
|---|---|---|
| oral | Film-coated tablet / 20 mg | colloidal silicon dioxide, hydroxypropyl methylcellulose, iron oxide red, iron oxide yellow, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polysorbate 80, pregelatinized starch, titanium dioxide. |
INDICATIONS AND CLINICAL USE
Famotidine (Acid Controller) Tablets is indicated for:
- the treatment of the following conditions where a controlled reduction of gastric secretion is required, such as acid indigestion, heartburn, sour or upset stomach;
- prevention of acid indigestion, heartburn, sour or upset stomach when associated with the consumption of food and/or beverage including nocturnal symptoms associated with the evening meal and expected to cause sleep disturbance.
CONTRAINDICATIONS
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container.
Cross sensitivity in this class of compounds has been observed. Therefore, Famotidine (Acid Controller) Tablets should not be administered to patients with a history of hypersensitivity to other H2-receptor antagonists.
WARNINGS AND PRECAUTIONS
General
In clinical trials, patients with other underlying acid gastrointestinal diseases
(e.g. duodenal ulcer, gastric ulcer) did not experience complications; in general, they did not exhibit a clinically significant deterioration in their condition. However, if patients have difficulty or pain on swallowing, severe vomiting, melaena (black stools) choking or chest pain, or if abdominal discomfort persists, patients should consult a physician to determine the underlying cause. Symptomatic response to therapy with famotidine does not preclude the presence of gastric malignancy.
Patients with severe coexisting illness should consult a physician before commencing therapy with Famotidine (Acid Controller) Tablets.
Patients consuming nonsteroidal anti-inflammatory drugs may have dyspepsia as a side effect of these medicines and should consult a physician or a pharmacist before taking Famotidine (Acid Controller) Tablets.
Patients over 40 who are experiencing heartburn for the first time, and patients who have noticed unintentional weight loss should consult a physician before using the product.
Further medical evaluation is required if therapy exceeds two weeks of continuous treatment, if two 14 day courses of treatment are needed at intervals of less than 6 weeks, or if heartburn is frequent (>3 times per week) and/or severe.
Gastrointestinal
Patients with a previous history of ulcer disease complications, those who are experiencing unintended weight loss in association with dyspeptic symptoms, and those who are middle- aged or older with new or recently changed dyspeptic symptoms should consult a physician before commencing therapy with Famotidine (Acid Controller) Tablets.
Renal
Patients with severe kidney disease should consult a physician before commencing therapy with Famotidine (Acid Controller) Tablets. A dosage adjustment may be necessary in patients with moderate or severe renal impairment (creatinine clearance less than 60 mL/min/1.48m2).
Since CNS adverse effects have been reported in patients with moderate and severe renal insufficiency, longer intervals between doses or lower doses may need to be used in patients with moderate (creatinine clearance 30 - 50 mL/min) or severe (creatinine clearance < 30 mL/min) renal insufficiency to adjust for the longer elimination half-life of famotidine (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics and DOSAGE AND ADMINISTRATION, Dosage Adjustment for Patients with Moderate or Severe Renal Insufficiency).
Special Populations
Pregnant Women: Reproductive studies have been performed in rats and rabbits at oral doses of up to 2000 and 500 mg/kg/day, respectively (approximately 2500 and 625 times the maximum recommended prescription human dose [80 mg], respectively), and have revealed no evidence of impaired fertility or harm to the fetus due to famotidine. There are, however, no adequate or well-controlled studies in pregnant women.
Since the safe use of famotidine in pregnant women has not been established, pregnant women should not use famotidine unless directed otherwise by a physician.
Nursing Women: Famotidine is detectable in human milk. Nursing mothers should either stop this drug or should stop nursing.
Pediatrics (<12 years of age): Safety and effectiveness in children have not been established. famotidine should not be administered to children under 12 years of age.
Geriatrics: No dosage adjustment is required based on age (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacokinetics). This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. (see PRECAUTIONS, Renal and DOSAGE AND ADMINISTRATION, Dosage Adjustment for Patients with Moderate or Severe Renal Insufficiency).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Famotidine has been demonstrated to be generally well tolerated.
Clinical Trial Adverse Drug Reactions
The following adverse reactions have been reported in ≥1% of patients using Famotidine (Acid Controller) Tablets. in controlled clinical trials (prevention or treatment): headache(6.9%), diarrhea (2.9%), upper respiratory infection (2.9%), vomiting (2.4%), constipation (2.0%), nausea (2.0%), pharyngitis (2.0%), flu-like illness (1.6%), back pain (1.2%) and rash (1.2%). These occurred with comparable frequency across treatment groups and control groups.
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Other reactions reported in patients using famotidine in controlled clinical trials at rates <1%. These observations are listed.
| Body as a Whole / Site Unspecified 1.0% | |
| Asthenia/Fatigue | 0.1% |
| Pain -abdominal | 0.3% |
| Pain -chest | 0.1% |
Each of the following at <0.1%: fever, infection-viral, pain-pelvic
Cardiovascular System 0.2%
Each of the following at <0.1%: extravasation, premature atrial contraction, premature ventricular contraction
Digestive System 1.7%
Dyspepsia 0.1%
Each of the following at <0.1%: erosive esophagitis, esophagitis, gingivitis and glossodynia
Musculoskeletal System 0.5%
Myalgia 0.1%
Pain - shoulder 0.1%
Each of the following at <0.1%: pain-foot, pain-knee, pain-neck
Nervous System and Psychiatric 2.4%
Anxiety 0.1%
Dizziness 0.1%
Each of the following at <0.1%: agitation, migraine
Respiratory System 1.3%
Sinusitis 0.1%
Each of the following at <0.1%: bronchitis, congestion -nasal, cough, dry throat, influenza, sinus disorder, sneezing, wheezing.
Skin and Skin Appendages 0.4%
Each of the following at <0.1% edema - angioneurotic, infection -skin, laceration, measles.
Special Senses 0.2%
Each of the following at <0.1%: eustachian tube disorder, hemorrhage- corneal, pain-ear.
Urogenital System 0.4%
Mass, breast 0.1%
Each of the following at <0.1%: benign prostatic hypertrophy, dysuria, hematuria, impotence, menstruation disorder, urinary frequency
Abnormal Hematologic and Clinical Chemistry Findings
Laboratory parameters may be affected during treatment with famotidine, but the changes are usually not considered serious. Among the laboratory changes that were reported during clinical trials were increases in AST, ALT, and WBC count, and decreases in hemoglobin and hematocrit. These changes were rarely of clinical significance.
No famotidine-treated patients/subjects had to be discontinued from therapy because of laboratory adverse experiences.
Post-Market Adverse Drug Reactions
During marketed use of prescription doses, which are higher than those recommended for non- prescription use, the following adverse reactions have been reported; urticaria, liver enzymes abnormalities, cholestatic jaundice, asthenia, fatigue, somnolence, abdominal discomfort and pain, abdominal pain upper, diarrhoea, dry mouth, nausea, vomiting, pruritus, rash, hypersensitivity, malaise, anaphylaxis, angioedema, malaise, and somnolence. Toxic epidermal necrolysis has been reported very rarely with H2-receptor antagonists. As with other H2-receptor antagonists, cases of bradycardia, A-V block and other arrhythmia have been reported rarely in patients treated with famotidine.
The following adverse reactions have been reported; however, a causal relationship to therapy with famotidine has not been established: agitation, confusion, hallucinations, depression, disorientation, mental disorder, insomnia, psychotic disorder, pruritus, alopecia, photosensitivity, Steven Johnson syndrome, hypotrichosis, neutropenia, anaemia, paraesthesia, dysgeusia, convulsions, syncope, grand mal seizures, rare cases of impotence, thrombocytopenia, pancytopenia, leukopenia, bone marrow depression and agranulocytosis.
Gynecomastia has been reported rarely. In most cases that were followed up, it was reversible after discontinuing treatment.
Post-Market Data
Adverse drug reactions (ADRs) identified during Post-marketing experience with famotidine are included in Table 1 below. The frequencies are provided according to the following convention based on spontaneous reporting rates:
Very common ≥1/10
Common ≥1/100 and <1/10
Rare ≥1/10,000 and < 1/1,000
Very rare <1/10,000
Not known (cannot be estimated from the available data)
Table 1: Adverse Drug Reactions Identified during Post-Marketing Experience with Famotidine for OTC use by Frequency Category Estimated from Clinical Trials
| SOC | ||
|---|---|---|
| Adverse Event Preferred Term | Frequency Category | |
Clinical Trials
| Spontaneous Reporting Rates | |||||
| Nervous System Disorders | |||||
| Dizziness | Uncommon* | Very rare | |||
| Asthenia, Fatigue | Uncommon* | Very rare | |||
| Somnolence | Rare* | Very rare | |||
| Gastrointestinal Disorders | |||||
| Abdominal discomfort and pain | Uncommon* | Very rare | |||
| Abdominal pain upper | Not known | Very rare | |||
| Diarrhea | Uncommon* | Very rare | |||
| Dry mouth | Rare* | Very rare | |||
| Nausea | Uncommon* | Very rare | |||
| Vomiting | Uncommon* | Very rare | |||
| Skin and Subcutaneous Tissue Disorders | |||||
| Pruritus | Rare* | Very rare | |||
| Rash | Uncommon* | Very rare | |||
| Urticaria | Not known | Very rare | |||
| Immune System Disorders | |||||
| Hypersensitivity | Not known | Very rare | |||
| Anaphylactic reaction | Not known | Very rare | |||
| Angioedema | Not known | Very rare | |||
| General Disorders and Administrative Site Conditions | |||||
| Malaise | Not known | Very rare | |||
*not significantly greater than Placebo (p<0.05)
In the above table, ADRs in the first frequency category column are presented based on incidence in adequately designed clinical trials or epidemiology studies, if available, or when incidence is unavailable, frequency category is listed as ‘Not known’. In the second frequency category column the same ADRs are presented frequency categories estimated from spontaneous reporting rates where the numerator represents total number reported Company Adverse Events under given Preferred Terms or medical concept and denominator represents exposure data calculated from sales data.
DRUG INTERACTIONS
Overview
Studies with famotidine in man, in animal models, and in vitro have shown no significant interference with the disposition of compounds metabolized by the hepatic microsomal enzymes, e.g., cytochrome P450 system. Compounds tested in man have included warfarin, theophylline, phenytoin, diazepam, aminopyrine and antipyrine. Indocyanine green as an index of hepatic blood flow and/or hepatic drug extraction has been tested and no significant effects have been found.
Concomitant use of aluminum hydroxide/magnesium hydroxide at commonly used doses, does not influence the pharmacodynamics or bioavailability of famotidine. Famotidine does not affect gastric alcohol dehydrogenase and, consequently, blood ethanol levels.
Patients should consult a physician before using this product together with any of the following drugs:
Itraconazole
Concomitant use of famotidine with the antifungal agent itraconazole results in significantly reduced peak and trough plasma concentrations of itraconazole, which may result in reduced antifungal efficacy.
Calcium carbonate
The hypophosphatemic effect of calcium carbonate is attenuated with concomitant use of H2-antagonists in patients undergoing chronic hemodialysis.
Drug-Food Interactions
Not known.
Drug-Herb Interactions
Not known
Drug-Laboratory Interactions
Not known
DOSAGE AND ADMINISTRATION
Dosing Considerations
Antacids may be given concomitantly if needed. It is not appropriate to use this product and other H2 Receptor Antagonists concomitantly.
Recommended Dose and Dosage Adjustment
Adults and children 12 years of age or older:
For relief of heartburn, acid indigestion and sour or upset stomach: The patient should take one tablet; to be swallowed whole with a glass of water. To prevent these symptoms, one tablet should be taken 10 – 15 minutes before eating food or drinking beverages that cause heartburn.
Dosage Adjustment for Patients with Moderate or Severe Renal Insufficiency
Patients with severe kidney disease should consult a physician before commencing therapy with Famotidine (Acid Controller) Tablets. A dosage adjustment may be necessary in patients with moderate or severe renal impairment (creatinine clearance less than 60 mL/min/1.48m2). In patients with moderate (creatinine clearance 30 – 50 mL/min), the elimination half-life of famotidine is increased. For patients with severe renal insufficiency, it may exceed 20 hours, reaching approximately 24 hours in anuric patients. Since CNS adverse reactions have been reported in patients with moderate and severe renal insufficiency, to avoid excess accumulation of the drug in patients with moderate or severe renal insufficiency, the dose of Famotidine (Acid Controller) Tablets may be reduced to half the dose or the dosing interval may be prolonged to 36-48 hours as indicated by the patient's clinical response.
Administration
The patient should not take more than 1 tablet at a time and the patient should not take more than two tablets in 24 hours. Therapy should not exceed two weeks of continuous treatment without medical consultation
OVERDOSAGE
Doses of up to 800 mg/day have been employed in patients with pathological hypersecretory conditions with no serious adverse effects. In the event of overdosage, treatment should be symptomatic and supportive. Unabsorbed material should be removed from the gastrointestinal tract, the patient should be monitored, and supportive therapy should be employed.
The oral LD50 of famotidine in male and female rats and mice was >5000 mg/kg.
Intentional exposure is defined as a purposeful action in patients who use a substance inappropriately for self-destructive or manipulative reasons, including suicides, suicide gestures, and attempts. The inappropriate use of famotidine (single agent) or with other agents for suicide attempts is very uncommon. There have been no reports that identified an overdose fatality with famotidine (single agent) or taken with other agents. For all overdose exposures, the duration of clinical effects, considered moderate or major, resolved in ≤3 days, the large majority and single- agent famotidine exposures resolved in ≤24 hours.
According to data from the Toxic Exposure Surveillance System (TESS) of the American Association of Poison Control Centers (AAPCC), of the single-agent famotidine exposures, the most common cardiovascular symptom was tachycardia (0.3%). For neurological symptoms, the proportions of subjects who experienced drowsiness/lethargy was 1.5%; headache, 0.6%; dizziness/vertigo, 1.0%; and agitated/irritable, 0.5%. Abdominal pain (1.9%), nausea (1.2%), vomiting (1.6%), and diarrhea (1.0%) were observed as gastrointestinal side effects. It is not known the extent to which the use of an emetic in hospital emergency rooms may have contributed to the occurrence of the symptoms nausea and vomiting.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Famotidine is a competitive inhibitor of histamine H2-receptors. The primary clinically important pharmacologic activity of famotidine is inhibition of gastric juice secretion. Famotidine reduces the acid and pepsin content, as well as the volume, of basal, nocturnal, and stimulated gastric secretion.
Pharmacodynamics
In both normal volunteers and hypersecretors, famotidine inhibited basal nocturnal and daytime gastric secretion. The duration of effect is up to 12 hours. In addition famotidine inhibits acid secretion stimulated by a variety of stimuli, such as pentagastrin and food.
Pharmacokinetics
Famotidine exhibits a linear pharmacokinetic profile for AUC and gastric pH in the 5- to 40-mg range. In this same range, associations have been demonstrated between mean plasma famotidine concentrations and mean inhibition of meal-stimulated acid secretion. However “area under the gastric pH-time curve” has not been shown to be directly associated or
For management of a suspected drug overdose, contact your regional Poison Control Centre.
correlated with heartburn relief.
Clinical studies have demonstrated that: famotidine prevents heartburn in patients with moderate to severe symptoms when taken before a meal. A dose response is demonstrated between 10 mg famotidine and 20 mg famotidine in successfully preventing acid-related symptoms and effectively relieving heartburn.
Famotidine is incompletely absorbed. The bioavailability of oral doses is 40-45%. Bioavailability may be slightly increased by food; however, this effect is of no clinical significance. Bioavailability of famotidine at recommended doses is not affected by customary doses of antacids. Famotidine undergoes minimal first-pass metabolism. After oral doses, peak plasma levels occur in 1-3 hours.
Plasma levels after multiple doses are similar to those after single doses in studies where patients received 20mg famotidine b.i.d. (8 a.m. and 5 p.m.) Iintravenously for a total of 15 doses, the last dose being administered in the morning of Day 8. Fifteen to 20% of famotidine in plasma is protein bound. Famotidine has an elimination half-life of 2.5-3.5 hours. Famotidine is eliminated by renal (65-70%) and metabolic (30-35%) routes. Renal clearance is 250-450 mL/min., indicating some tubular excretion.
Twenty-five to 30% of an oral dose and 65-70% of an intravenous dose are recovered in the urine as unchanged compound. The only metabolite identified in man is the S-oxide. There is a close relationship between creatinine clearance values and the elimination half-life of famotidine. In patients with severe renal insufficiency, i.e., creatinine clearance less than 30mL/min., elimination half-life of famotidine may exceed 20 hours (see DOSAGE AND ADMINISTRATION). In elderly patients, there are no clinically significant age-related changes in the pharmacokinetics of famotidine. However, in elderly patients with decreased renal function, the clearance of the drug may be decreased (see PRECAUTIONS, Special Populations, Geriatrics).
Absorption: The absorption of famotidine was studied in two animal species. Absorption was 28% in the rat and 43% in the dog.
Distribution: The distribution of famotidine was studied in two animal species. The plasma half-life in dogs was 2.5 hours, which was unchanged after repeated doses, indicating no tendency for the drug to accumulate. In rats, the highest levels of radioactivity after an oral dose of famotidine were found in the gastrointestinal tract, kidneys, liver, submandibular glands, arteries, epiphyseal membrane, fascia, and uvea. The distribution pattern was not affected on repeated dosing. Famotidine did not effectively cross the blood-brain or placental barrier of rats. It was present in rat milk.
Metabolism: The only metabolite of famotidine in rat and dog urine was the sulfoxide derivative, which was present in minor amounts.
Excretion: Urinary and fecal excretion of radioactivity in rats accounted for 28% and 70%, respectively, of an oral dose, compared to 83% and 17% respectively, of an intravenous dose. About 2.4% of the dose in rats was excreted in the bile. Dogs excreted 45% of an oral dose in the urine, compared to 100% of an intravenous dose.
Effects on Liver Microsomal Drug-Metabolizing Enzymes
Famotidine did not affect pentobarbital or hexobarbital sleeping times and it did not affect ascorbic acid excretion, suggesting that famotidine does not induce drug-metabolizing enzymes. Famotidine caused none of the changes induced by cimetidine on the pharmacokinetics of diazepam, warfarin, and propranolol. Famotidine produced only minimal suppression of aminopyrine and diazepam N-demethylase activity in vitro, and showed little affinity for testosterone hydroxylases of mouse liver in vitro.
Gastrointestinal Effects other than Antisecretory
Famotidine prevented gastric erosions induced in rats by cold restraint, water immersion, pyloric ligation, or drugs such as acetylsalicylic acid, histamine or prednisolone; also duodenal ulcers caused by cysteamine and mepirizole. It also significantly accelerated the healing of the gastric lesions induced by acetic acid and the duodenal ulcers produced by mepirizole.
The antiulcer effect of famotidine plus magnesium and aluminum hydroxides was greater than the sum of the effects of these drugs used separately.
Famotidine inhibited the gastric lesions and hemorrhage resulting from blood removal and histamine injection in anesthetized rats.
In normal rats, famotidine had no effect on the concentration of gastric mucosal histamine, but it did reduce the levels of cAMP, particularly in response to histamine stimulation.
In anaesthetized cats, famotidine had no effect on the intragastric electropotential when tested at intragastric doses more than ten-fold greater than those required to block gastric secretion maximally.
Cardiorenal Effects
The cardiorenal effects of famotidine were studied in dogs and rats. Ten mg/kg of famotidine administered orally were without effect on the blood pressure of spontaneously hypertensive rats. In anaesthetized dogs, intravenous administration of 1.0 and 4.0 mg/kg of famotidine was without effect on cardiovascular parameters relating to the autonomic nervous system, blood pressure, heart rate, or respiratory function. In conscious dogs, an oral dose of 10 mg/kg was without diuretic effect.
Central Nervous System Effects
The effects of famotidine on the central nervous system were studied in squirrel monkeys, mice, and cats. In monkeys famotidine had a bidirectional effect on lever pressing (avoidance response) causing an increase at the low dose (1.0 mg/kg p.o.) and a small decrease at 9 mg/kg. In mice following intraperitoneal administration of 6 to 150 mg/kg no overt behavioral signs or symptoms of central nervous system activity were observed. In mice famotidine was not active as an antagonist of the CNS actions of TRH, neurotensin, substance P, or amphetamine.
Famotidine was free of major or minor tranquilizing, anticonvulsant, anticholinergic, ganglionic blocking, or dopaminergic activity. In cats, famotidine did not affect the EEG or arousal response but did prolong the duration of hippocampal after-discharge. Only 4% of the plasma concentration of the drug was detected in the cerebrospinal fluid.
STORAGE AND STABILITY
Bottles should be stored between 15°C - 30°C in well-closed, light-resistant containers
DOSAGE FORMS, COMPOSITION AND PACKAGING
Each film-coated tablet for oral administration contains 20 mg of famotidine and the following non-medicinal ingredients: colloidal silicon dioxide, hydroxypropyl methylcellulose, iron oxide red, iron oxide yellow, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polysorbate 80, pregelatinized starch, titanium dioxide.
Famotidine (Acid Controller) Tablets is available as :
20 mg -D-shaped, buff coloured, biconved, film-coated tablets engraved 'novo' on one side and 20 on the other. Available in bottles of 100.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: famotidine
Chemical name: N'-(aminosulfonyl)-3-[[[2-[(diaminomethylene)amino]-4- thiazolyl]methyl]thio] Propanimidamide.
Molecular formula and molecular mass: C8H15N7O2S3 / 337.44 g/mol Structural formula:
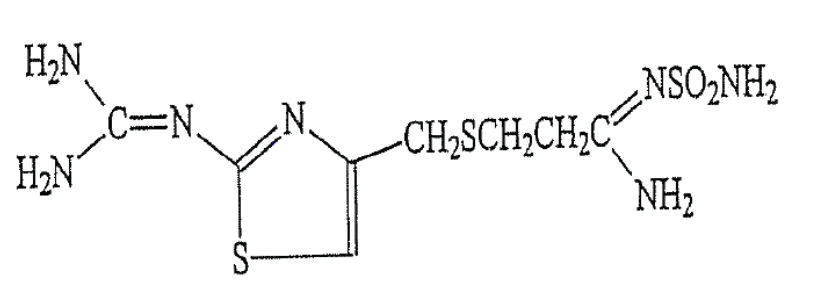
Physicochemical properties: Famotidine is a white to pale yellow crystalline compound that is freely soluble in glacial acetic acid, slightly soluble in methanol, very slightly soluble in water and practically insoluble in ethanol.
CLINICAL TRIALS
Comparative Bioavailability Studies
A single dose, two-way crossover comparative bioavailability study of FAMOTIDINE (ACID CONTROLLER) TABLETS 20 mg tablets (Teva Canada Limited) with MAXIMUM STRENGTH PEPCID AC® 20 mg tablets (Merck, Sharp & Dohme, Canada) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Famotidine (2 x 20 mg) Geometric Mean Arithmetic Mean (CV%) | |||||||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval | |||||
AUCT (ng·h/mL) | 594.9 635.2 (34) | 604.5 646.4 (34) | 98 | 83 – 117 | |||||
AUCI (ng·h/mL) | 663.4 699.1 (31) | 667.6 714.0 (34) | 99 | 85 – 116 | |||||
| Cmax (ng/mL) | 114.4 122.1 (37) | 110.2 120.3 (42) | 104 | 88 – 123 | |||||
| Tmax3 (h) | 2.6 (31) | 2.5 (27) | |||||||
T1/2 3 (h) | 3.0 (23) | 3.3 (24) | |||||||
1 FAMOTIDINE (ACID CONTROLLER) TABLETS(famotidine) tablets, 20 mg (Teva Canada Limited)
2 MAXIMUM STRENGTH PEPCID AC® (famotidine) tablets, 20 mg (Merck, Sharp & Dohme, Canada)
3 Expressed as the arithmetic mean (CV%) only
DETAILED PHARMACOLOGY
- I. ANIMAL PHARMACOLOGY
Famotidine inhibits gastric secretion evoked by histamine and other secretagogues. In dogs, the ED50 was 0.03 mg/kg after oral or intravenous administration of famotidine. An oral dose of 2.1 mg/kg in dogs inhibited gastric secretion for at least 24 hours. An oral dose of 3 mg/kg one hour prior to feeding inhibited the acid response in dogs during a 4-hour post feeding period by an average of 96%.
Mechanism of Action
Famotidine is a specific, competitive, H2-receptor antagonist. There was no effect in vitro on responses mediated by H1-histamine, beta1-adrenergic, or cholinergic receptors. Famotidine was inactive in radioligand binding to dopaminergic, neuroleptic, serotonergic, adrenergic, cholinergic, and purinergic sites. Famotidine was also inactive in an androgen receptor assay.
The interaction between famotidine and H2-receptors is tissue-dependent. In guinea pig lungs and rabbit gastric glands the effects of famotidine were surmountable and readily reversible on washout, indicating classic competitive inhibition at the H2-receptor sites. However, in guinea pig atria, famotidine acted as a non-competitive H2 antagonist, and recovery after washout of famotidine was retarded.
II. HUMAN PHARMACOLOGY
After oral administration, a dose-response relationship was clearly demonstrated from 10 mg and 20 mg famotidine in terms of raising gastric pH between and after meals. Famotidine doses of 10 mg and 20 mg were demonstrated to produce a statistically significant effect on gastric pH as compared to placebo. The maximum effect as measured by AUC (intragastric pH/hour) was seen with famotidine 20 mg. The mean AUC for 20mg famotidine, 10mg famotidine and placebo were 2.64, 2.13 and 1.35 respectively. The maximum effect as measured by percentage of intragastric pH values >3 (12 hour interval ) was seen with famotidine 20mg. The values for 20mg famotidine, 10mg famotidine and placebo were 32.65%, 21.37% and 5.83% respectively. Famotidine was well-tolerated at all dose levels.
Fasting and postprandial serum gastrin levels may be slightly elevated during periods of drug antisecretory effect, and with chronic therapy an increase in gastric bacterial flora may occur. It has been postulated that H2RAs and proton pump inhibitors (PPIs) could increase susceptibility to pulmonary infections by increasing gastric pH. However the safety surveillance database does not support this issue would be a concern when famotidine 20mg is used acutely as directed in the management of heartburn. Gastric emptying and exocrine pancreatic function are not affected by famotidine.
Other Effects
Systemic pharmacologic effects of famotidine involving the CNS, cardiovascular, respiratory or endocrine systems have not been found to date. Serum prolactin levels do not rise after intravenous bolus doses of 20 mg of famotidine and no antiandrogenic effects have been detected.
TOXICOLOGY
| Acute Toxicity Species | Sex | Route | LD50 (mg/kg) |
|---|---|---|---|
| Mouse | M | P.O.* | 4,684 |
| F | P.O.* | 3,233 | |
| Mouse | M | I.V. (4%) | 254 |
| F | I.V. (4%) | 358 | |
| Rat | M | P.O.* | 4,907 |
| F | P.O.* | 4,049 | |
| Rat | M | I.P. | 987 |
| F | I.P. | 814 |
*In solution (acidic, 50-55°C deionized water).
Subacute and Chronic Toxicity
Famotidine is well tolerated by both rats and dogs at doses of 2 g/kg twice a day orally in subacute studies and at doses up to 1000 or 2000 mg/kg/day for one year in these species. Eosinophilic cytoplasmic granularity of gastric chief cells was seen at a higher incidence in rats given 200 mg/kg/day or more of the compound compared to controls. This is considered as a secondary effect due to the exaggerated pharmacologic activity of the compound and at these extremely high dosage levels and is considered of no toxicologic significance. In a 106-week study in rats designed to study the carcinogenic potential of the compound, this gastric change did not progress to hyperplasia or neoplasia. Similarly, mice (given the compound for 92 weeks) showed no evidence of a neoplastic potential. Based on the results from studies performed using pharmacologically-related compounds, this change was fully reversible.
Intravenous administration of famotidine was well tolerated by rats for 13 weeks at dosage levels of up to 20 mg/kg/day and by dogs, except for occasional emesis, at dosage levels of up to
10 mg/kg/day for 5 to 26 weeks.
Reproduction Studies
In studies with rats given oral doses of up to 2000 mg/kg/day or intravenous doses of up to 200 mg/kg/day (approximately 2500 and 250 times the maximum recommended prescription human dose, respectively), fertility and reproductive performance were not affected.
Famotidine given orally to pregnant rats up to 2000 mg/kg/day or intravenously at dosage levels up to 200 mg/kg/day, from Days 7 to 17 of pregnancy did not reveal any evidence of embryolethality or teratogenicity.
Oral administration of famotidine to pregnant rabbits from Days 6 to 18 of pregnancy at dosage levels up to 500 mg/kg/day revealed no evidence of embryolethality or teratogenicity.
Mutagenicity
Famotidine was tested in a reverse-mutation test (Ames test) using Salmonella typhimurium and
Escherichia coli with and without metabolic activation. No mutagenic potential was seen. These same studies were performed with famotidine/sodium, nitrite reaction mixture and nitroso derivatives of famotidine and they were also negative. Famotidine and C-nitroso derivatives of famotidine were tested in the rec-assay using Bacillus subtilis H17 and M45 and the tests were negative for DNA-damaging capacity of the compounds. In in vivo studies in mice, a micronucleus test and a chromosomal aberration test, no evidence of a mutagenic effect was seen.
Carcinogenicity
A 92-week oral carcinogenicity study was conducted in mice at doses of 20, 200 and 2000 mg/kg/day. No evidence of a carcinogenic potential was seen. A 106-week oral carcinogenicity study in rats given doses of 20, 200 and 2000 mg/kg/day did not reveal any carcinogenic potential for famotidine.
Special Studies
The effects of famotidine on the thyroid of rats were evaluated after five weeks of oral administration at doses up to 2000 mg/kg/day. No evidence of treatment-related alterations of serum thyroid hormone levels, thyroid weight or the microscopic appearance were seen after administration of famotidine.
In immunogenicity studies, no effect on the production of IgE antibodies was seen in the sera of mice which were injected, once intraperitoneally, with famotidine alone (up to 2 mg/8 mL/kg) or coupled with either mouse serum albumin or ovalbumin. The sera were used to measure passive cutaneous anaphylaxis in rats which were then challenged with solutions of antigens similar to those antigens used for the initial dose in mice. Similarly, no evidence of an anaphylactic reaction was seen in guinea pigs challenged intravenously with famotidine after initiating doses (three times, subcutaneously, at six-day intervals) of up to 10 mg/mL.
REFERENCES
- 1. Hayakawa A, Che K, Miyoshi A, Harasawa S, Miwa T, Makabatake T. Properties of famotidine in relation to safety. Ital J Gastroenterol 1984;16:174- 176.
- 2. McCallum RW, Kuljian B, Chremos AN, Tupy-Visich MA, Huber PB. Prolonged gastric antisecretory effect of a novel H2-receptor inhibitor, MK-208. Gastroenterology (in Soc. Proc.) 1983;84:1245.
- 3. Barzaghi N, Gratti G, Crema F, Perucca E. Impaired bioavailability of famotidine given concurrently with a potent antacid. J Clin Pharmacol 1989;29:670-72.
- 4. Echizen H, Ishizaki T. Clinical pharmacokinetics of famotidine. Clin Pharmacokin 1991;21:178-94.
- 5. Lin JH, Chremos AN, Kanovsky SM, Schwartz S, Yeh KC, Kahn J. Effects of antacids and food on absorption of famotidine. Br J Clin Pharmacol 1987:24:551-53
- 6. Laheij RJF, Sturkenboom MCJM, Hassing RJ, Dieleman J, Stricker BHC, Jansen JBMJ. Risk of Community -Acquired Pneumonia and Use of Gastric-Suppressive Drugs JAMA 2004: 292 (16): 1955-1960.
- 7. Product Monograph for MAXIMUM STRENGTH PEPCID AC®. McNeil Consumer Healthcare, division of Johnson & Johnson Inc. Canada. (control# 225990) May 24, 2019.
- 8. A comparative two-way, single-dose bioavailability study of famotidine 20 mg tablets in fasting volunteers. Completed October 1996. Data on file at Teva Canada Limited.