


Product Monograph - Fondaparinux Sodium Injection
2 CONTRAINDICATIONS
Fondaparinux Sodium Injection is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see Dosage Forms, Strengths, Composition and Packaging.
- Thrombocytopenia associated with a positive in vitro test for anti-platelet antibody in the presence of fondaparinux sodium.
- Active clinically significant bleeding.
- Acute bacterial endocarditis.
3 DOSAGE AND ADMINISTRATION
- 3.1 Dosing Considerations
Use in Patients with Renal Insufficiency
The risk of hemorrhage increases with increasing renal insufficiency. Fondaparinux Sodium Injection should be used with caution in patients with moderate renal insufficiency (creatinine clearance 30–50 mL/min) (see ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency). In severe renal impairment, the use of Fondaparinux Sodium Injection should be avoided or, if the physician determines that the benefit outweighs the risk, Fondaparinux Sodium Injection should only be used with caution.
Renal function should be assessed periodically in patients receiving the drug. For prophylactic use following orthopedic surgery, Fondaparinux Sodium Injection should be discontinued immediately in patients who develop severe renal insufficiency or labile renal function while on therapy. After discontinuation of Fondaparinux Sodium Injection, its anticoagulant effects may persist for 2-4 days in patients with normal renal function (i.e. at least 3-5 half-lives). The anticoagulant effects of Fondaparinux Sodium Injection may persist even longer in patients with renal insufficiency.
Use in Patients with Hepatic Insufficiency
No dose adjustment is recommended in patients with mild to moderate hepatic impairment, based upon single-dose pharmacokinetic data. Pharmacokinetic data are not available for patients with severe hepatic impairment. Patients with hepatic impairment may be particularly vulnerable to bleeding during Fondaparinux Sodium Injection therapy. Observe these patients closely for signs and symptoms of bleeding (see WARNINGS AND PRECAUTIONS).
Use in Pediatric Patients
Health Canada has not authorized an indication for pediatric (<17 years of age) use.
Use in Geriatric Patients
Use with caution in elderly patients (see WARNINGS AND PRECAUTIONS, Geriatrics, and
ADVERSE REACTIONS, Geriatrics).
Use in Patients with Low Body Weight
For patients of body weight < 50 kg, Fondaparinux Sodium Injection should be used with caution (see WARNINGS AND PRECAUTIONS, Low Body Weight).
3.2 Recommended Dose and Dosage Adjustment Prophylaxis of VTE following orthopedic surgery
The recommended dose of Fondaparinux Sodium Injection is 2.5 mg once daily administered post-operatively by subcutaneous injection.
After hemostasis has been established, the initial dose should be given no earlier than 6 hours after surgical closure. In clinical studies, 99% of the patients had received the initial dose of Fondaparinux Sodium Injection by 18 hours after surgical closure. Administration before 6 hours after orthopedic surgery has been associated with an increased risk of major bleeding. The timing of the first dose of Fondaparinux Sodium Injection following surgery requires strict adherence (see WARNING AND PRECAUTIONS, Hemorrhage, and Peri-Operative Considerations; ACTION AND CLINICAL PHARMACOLOGY).
The usual duration of prophylactic therapy with Fondaparinux Sodium Injection is 7 ± 2 days. Treatment should be continued for as long as the risk of VTE persists. In patients for whom extended prophylaxis is indicated, administration of Fondaparinux Sodium Injection in or out of the hospital up to an additional 24 days is recommended. In clinical trials of extended prophylaxis, a total of 32 days (peri-operative and extended prophylaxis) has been tolerated.
Prophylaxis of VTE following abdominal surgery
The recommended dose of Fondaparinux Sodium Injection is 2.5 mg once daily administered post-operatively by subcutaneous injection after hemostasis has been established.
The initial dose should be given 6 to 8 hours after surgery. Administration before 6 hours after abdominal surgery has been associated with an increased risk of major bleeding. The timing of the first dose of Fondaparinux Sodium Injection following surgery requires strict adherence (see WARNING AND PRECAUTIONS, Hemorrhage, and Peri-Operative Considerations; ACTION AND CLINICAL PHARMACOLOGY).
The usual duration of administration is 5 to 9 days, and up to 10 days of Fondaparinux Sodium Injection has been administered.
Treatment of DVT and PE
The recommended dose of Fondaparinux Sodium Injection is 5 mg (body weight < 50 kg), 7.5 mg (body weight 50-100 kg) or 10 mg (body weight > 100 kg) by subcutaneous injection once daily.
Concomitant oral anticoagulation treatment should be initiated as soon as possible, usually within 72 hours. Fondaparinux Sodium Injection treatment should be continued for at least 5 days and until a therapeutic oral anticoagulant effect is established (INR 2.0 to 3.0).
The average duration of administration is 7 days. In controlled clinical trials administration of fondaparinux sodium for up to 26 days to a small number of patients has been well tolerated.
Management of Unstable Angina/Non-ST Segment Elevation Myocardial Infarction (UA/NSTEMI)
The recommended dose of Fondaparinux Sodium Injection is 2.5 mg once daily, administered by subcutaneous injection. Treatment should be initiated as soon as possible following diagnosis and may be continued for up to 8 days or until hospital discharge.
If a patient is to undergo percutaneous coronary intervention (PCI) while being treated with Fondaparinux Sodium Injection, an effective anti-thrombin regimen such as unfractionated heparin (UFH) should be administered as an adjunct to PCI, as per standard practice, taking into account the patient’s potential risk of bleeding, including the time since the last dose of Fondaparinux Sodium Injection (see WARNINGS AND PRECAUTIONS, Risk of catheter thrombosis during PCI, and Hemorrhage).
The timing of the next dose of subcutaneous Fondaparinux Sodium Injection after sheath removal should be based on clinical judgment. In the UA/NSTEMI clinical trials treatment with Fondaparinux Sodium Injection was restarted no earlier than 2 hours after sheath removal.
In patients who are to undergo coronary artery bypass graft (CABG) surgery, Fondaparinux Sodium Injection where possible, should not be given during the 24 hours before surgery and may be restarted 48 hours post-operatively.
Management of ST Segment Elevation Myocardial Infarction (STEMI)
The recommended dose of Fondaparinux Sodium Injection is 2.5 mg once daily. The first dose of Fondaparinux Sodium Injection is administered intravenously and subsequent doses are administered by subcutaneous injection. Treatment should be initiated as soon as possible following diagnosis and continued for up to 8 days or until hospital discharge.
Fondaparinux Sodium Injection should not be used if primary PCI is the planned reperfusion therapy (see INDICATIONS, WARNINGS AND PRECAUTIONS, Risk of catheter thrombosis during PCI). Fondaparinux Sodium Injection is indicated for use in patients who are managed with thrombolytics or who initially are to receive no form of reperfusion therapy.
If a patient is to undergo subsequent PCI while being treated with Fondaparinux Sodium Injection, an effective anti- thrombin regimen such as unfractionated heparin (UFH) should be administered as an adjunct to PCI as per standard practice, taking into account the patient’s potential risk of bleeding, including the time since the last dose of Fondaparinux Sodium Injection (see WARNINGS AND PRECAUTIONS, Risk of catheter thrombosis during PCI, and Hemorrhage).
There are limited data on the use of UFH during non-primary PCI in STEMI patients treated with fondaparinux (see CLINICAL TRIALS). In those patients with STEMI who underwent non- primary PCI in OASIS-6 less than 6 hours after the last dose of fondaparinux, the median dose of UFH was 5000 IU and the incidence of major bleeding was 4.1% (2/49). In those patients who underwent non-primary PCI 6-24 hours after the last dose of fondaparinux, the median dose of UFH was 8000 IU and the incidence of major bleeding was 2% (2/98).
The timing of the next dose of subcutaneous fondaparinux after sheath removal should be based on clinical judgment. In the STEMI clinical trials treatment with fondaparinux was restarted no earlier than 3 hours after sheath removal.
In patients who are to undergo coronary artery bypass graft (CABG) surgery, fondaparinux where possible, should not be given during the 24 hours before surgery and may be restarted 48 hours post-operatively.
Health Canada has not authorized an indication for pediatric (<17 years of age) use. (see Indications, Pediatrics)
3.3 Administration
Fondaparinux Sodium Injection is intended for use under a physician’s guidance. Patients may self-inject only if their physician determines that it is appropriate, and with medical follow-up as necessary. Proper training in subcutaneous injection technique should be provided.
Subcutaneous administration:
Administration is by subcutaneous injection only. Do not inject Fondaparinux Sodium Injection intramuscularly.
To avoid the loss of medicinal product when using the pre-filled syringe do not expel the air bubble from the syringe before the injection. For step-by-step instructions for use, please see CONSUMER INFORMATION.
Intravenous administration:
For STEMI patients treated with Fondaparinux Sodium Injection, the initial dose is to be administered intravenously. Administration should be through an existing intravenous line either directly or using a small volume (25 mL or 50 mL) 0.9% saline minibag as the first dose in the treatment of STEMI.
To avoid the loss of medicinal product when using the pre-filled syringe, do not expel the air bubble from the syringe before the injection. The intravenous tubing should be well flushed with saline after the administration of Fondaparinux Sodium Injection to ensure that all of the medicinal product is administered. If administered via a minibag, the infusion should be given over 1 to 2 minutes.
If Fondaparinux Sodium Injection is added to a 0.9% saline minibag it should be infused immediately, but can be stored between 15-30 °C for up to 24 hours. Minibags are typically composed of a variety of polymers including PVC, polyethylene, polypropylene, or styrene-ethylene-butadiene, individually or in combination.
In the absence of compatibility studies, Fondaparinux Sodium Injection must not be mixed with other medicinal products.
3.4 Missed Dose
Never inject a double dose to make up for forgotten individual doses. The management depends on clinical judgement.
4 OVERDOSAGE
Hemorrhage is the major clinical sign of overdosage.
Overdosage of Fondaparinux Sodium Injection, associated with bleeding complications, should lead to treatment discontinuation, a search for the primary cause of bleeding, and initiation of appropriate therapy, which may include surgical hemostasis, blood replacement, fresh plasma transfusion, or plasmapheresis.
Minor bleeding rarely requires specific therapy, and reducing or delaying subsequent doses of Fondaparinux Sodium Injection is usually sufficient.
For management of a suspected drug overdose, contact your regional poison control centre.
5 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table – Dosage Forms, Strengths, Composition and Packaging.
| Route of Administration | Dosage Form / Strength/Composition | All Non-medicinal Ingredients |
| Subcutaneous | Injection / 2.5 mg / 0.5 mL 5 mg / 0.4 mL 7.5 mg / 0.6 mL 10 mg / 0.8 mL | Isotonic solution of sodium chloride and water for injection. Also contains sodium hydroxide or hydrochloric acid for pH adjustment. |
| Intravenous | Injection / 2.5 mg / 0.5 mL | |
Fondaparinux Sodium Injection, supplied as a sterile injectable solution for subcutaneous and intravenous use, is available in the following strengths and package sizes:
Package of 10:
2.5 mg Fondaparinux Sodium Injection in 0.5 mL single dose prefilled syringe, affixed with a 27-gauge x ½ inch needle with a blue plunger rod.
5 mg Fondaparinux Sodium Injection in 0.4 mL single dose pre-filled syringe, affixed with a 27-gauge x ½ inch needle with an orange plunger rod.
7.5 mg Fondaparinux Sodium Injection in 0.6 mL single dose pre-filled syringe, affixed with a 27-gauge x ½ inch needle with a magenta plunger rod.
10 mg Fondaparinux Sodium Injection in 0.8 mL single dose pre-filled syringe, affixed with a 27-gauge x ½ inch needle with a violet plunger rod.
Single use. Discard unused portion. Latex Free Stopper and Needle Shield - Preservative Free
As with all parenteral drug products, syringes should be inspected visually for clarity, particulate matter, precipitate, discolouration and leakage prior to administration. Solutions showing haziness, particulate matter, precipitate, discolouration or leakage should not be used.
6 WARNINGS AND PRECAUTIONS
General
Fondaparinux Sodium Injection must be administered only by the subcutaneous (SC) or intravenous (IV) route. Fondaparinux Sodium Injection must not be administered intramuscularly.
Carcinogenesis and Mutagenesis
See TOXICOLOGY, Carcinogenicity and Mutagenicity.
Cardiovascular
Risk of catheter thrombosis during PCI
In patients undergoing any percutaneous coronary intervention (PCI), the use of Fondaparinux Sodium Injection as the sole anticoagulant during PCI is not recommended because of an increased risk of guiding catheter thrombosis. An effective anti-thrombin regimen such as unfractionated heparin (UFH) should be used as an adjunct to PCI, according to standard practice (see DOSAGE AND ADMINISTRATION, and DETAILED PHARMACOLOGY).
In STEMI patients undergoing primary PCI for reperfusion, the use of Fondaparinux Sodium Injection prior to and during PCI is not recommended (see ADVERSE REACTIONS, Management of STEMI, Risk of catheter thrombosis during PCI, and DOSAGE AND ADMINISTRATION).
Clinical trials have shown a low but increased risk of guiding catheter thrombosis in patients treated solely with fondaparinux sodium for anticoagulation during PCI compared to control (see ADVERSE REACTIONS, Management of UA/NSTEMI and Management of STEMI, Risk of catheter thrombosis during PCI). Incidences during PCI in UA/NSTEMI were 1.00% with fondaparinux sodium, 0.32% with enoxaparin alone, and 0.16% with enoxaparin with adjunctive UFH. In fondaparinux-treated UA/NSTEMI patients randomized to receive one of two dosing regimens of adjunctive UFH during PCI, the incidences of catheter thrombus were reported to range from 0.1% to 0.5%, depending on the UFH dose administered (For further details, see ADVERSE REACTIONS, Management of UA/NSTEMI, Risk of catheter thrombosis during PCI). In patients with STEMI undergoing primary PCI, incidences were 1.18% with fondaparinux sodium and 0% with UFH. Use of Fondaparinux Sodium Injection during primary PCI is not recommended.
It is to be expected that the risk of peri-procedural myocardial infarction (MI) may be increased in patients who develop guiding catheter thrombosis, irrespective of anticoagulant used (see ADVERSE REACTIONS, Management of UA/NSTEMI and Management of STEMI, Risk of catheter thrombosis during PCI).
Driving and Operating Machinery
Due caution should be exercised when driving or operating a vehicle or potentially dangerous machinery.
Hematologic Hemorrhage
Fondaparinux Sodium Injection, like other antithrombotic drugs, should be used with caution in patients who have an increased risk of hemorrhage, such as those with congenital or acquired bleeding disorders, active ulcerative gastrointestinal disease and recent intracranial hemorrhage or shortly after brain, spinal, or ophthalmological surgery.
Risk of hemorrhage is expected to increase with decreasing renal function (see ADVERSE REACTIONS). Appropriate caution should be exercised in patients with moderate to severe renal impairment (see WARNINGS AND PRECAUTIONS, Renal).
Prophylaxis and Treatment of VTE
Agents that may enhance the risk of hemorrhage, with the exception of vitamin K antagonists used concomitantly for treatment of VTE, should be discontinued prior to initiation of Fondaparinux Sodium Injection therapy. If co-administration is necessary, close monitoring may be appropriate (see DRUG INTERACTIONS).
Prophylaxis of VTE following orthopedic or abdominal surgery (timing of first fondaparinux injection)
The timing of the first dose of Fondaparinux Sodium Injection following surgery requires strict adherence. The first dose should be given no earlier than 6 hours following surgical closure, and only after hemostasis has been established. Administration before 6 hours has been associated with an increased risk of major bleeding (see DOSAGE and ADMINISTRATION). Patient groups at particular risk are those older than 75 years of age, body weight of less than 50 kg or renal impairment with creatinine clearance less than 50 mL/min.
Management of UA/NSTEMI, STEMI
Fondaparinux Sodium Injection should be used with caution in patients who are being treated concomitantly with other therapies that increase the risk of hemorrhage (such as GPIIb/IIIa inhibitors or thrombolytics).
Thrombocytopenia
Thrombocytopenia of any degree should be monitored closely. If the platelet count falls below 50,000/mm3, Fondaparinux Sodium Injection should be discontinued. Fondaparinux Sodium Injection is contraindicated in patients with thrombocytopenia associated with a positive in vitro test for anti-platelet antibody in the presence of fondaparinux.
Rare spontaneous reports of heparin-induced thrombocytopenia (HIT) in patients treated with fondaparinux have been received.
Prophylaxis of VTE following orthopedic or abdominal surgery
Thrombocytopenia can occur with the administration of Fondaparinux Sodium Injection following any major surgical procedure. Moderate thrombocytopenia (platelet counts between 100,000/mm3 and 50,000/mm3) occurred at a rate of 3.0% in patients given fondaparinux sodium 2.5 mg in the peri- operative orthopedic and abdominal surgery clinical trials. Severe thrombocytopenia (platelet counts less than 50,000/ mm3) occurred at a rate of 0.2% in patients given 2.5 mg in peri- operative clinical trials.
Treatment of DVT and PE
Moderate thrombocytopenia occurred at a rate of 0.5% in patients given the fondaparinux sodium treatment regimen in the DVT and PE treatment clinical trials. Severe thrombocytopenia occurred at a rate of 0.04% in patients given the fondaparinux sodium treatment regimen.
Hepatic
There is no evidence that fondaparinux is metabolized or eliminated hepatically. Following a single subcutaneous dose of 7.5 mg of fondaparinux sodium in patients with moderate hepatic impairment (Child-Pugh Category B) compared to subjects with normal liver function, changes from baseline in aPTT, PT/INR, and antithrombin III were similar in the two groups (see ACTION AND CLINICAL PHARMACOLOGY, Special Populations and Conditions, Hepatic Insufficiency). However, a higher incidence of hemorrhage was observed in subjects with moderate hepatic impairment than in normal subjects, especially mild hematomas at the blood sampling or injection site. The pharmacokinetics of fondaparinux have not been studied in patients with severe hepatic impairment. The use of Fondaparinux Sodium Injection should be considered with caution because of an increased risk of bleeding due to a deficiency of coagulation factors in patients with severe hepatic insufficiency. Thus, in patients with severe hepatic insufficiency, Fondaparinux Sodium Injection should be used only with care.
Monitoring, Laboratory and Coagulation Tests
Since the international standards of heparin or low molecular weight heparins (LMWH) are not appropriate calibrators, the activity of fondaparinux sodium is expressed in milligrams (mg) of the fondaparinux and cannot be compared with activities of heparin or LMWH.
At the 2.5 mg dose, Fondaparinux Sodium Injection does not have a clinically relevant effect on routine coagulation tests such as activated partial thromboplastin time (aPTT), activated clotting time (ACT) or prothrombin time (PT)/International Normalized Ratio (INR) tests in plasma. When administered at the recommended prophylactic dose, routine coagulation tests such as PT and aPTT are relatively insensitive measures of Fondaparinux Sodium Injection activity, and therefore unsuitable for monitoring. Although monitoring of Fondaparinux Sodium Injection is generally not required, the anti-Factor Xa assay is the preferred test to measure the anti-coagulant activity of Fondaparinux Sodium Injection. Only fondaparinux can be used to calibrate the anti-Xa assay (see ACTION AND CLINICAL PHARMACOLOGY, Mechanism of Action).
If during Fondaparinux Sodium Injection therapy, unexpected changes in coagulation parameters or major bleeding occurs, Fondaparinux Sodium Injection should be discontinued and a search for other causes such as concomitant medications that could interfere with coagulation, should be undertaken.
Peri-Operative Considerations
There have been cases of intra-spinal hematomas with the concurrent use of antithrombotics (i.e. low molecular weight heparins) and spinal/epidural anaesthesia resulting in long-term or permanent paralysis. The risk of these events may be higher with the use of post-operative indwelling epidural catheters or by the concomitant use of drugs affecting hemostasis: nonsteroidal anti-inflammatory drugs (NSAIDS), platelet inhibitors, or other drugs affecting coagulation. The risk also appears to be increased by traumatic or repeated epidural or spinal procedure. Fondaparinux Sodium Injection should only be used concurrently with spinal/epidural anaesthesia when the therapeutic benefits to the patients outweigh the possible risks. Careful vigilance for neurological signs is recommended with rapid diagnosis and treatment, if signs occur.
Renal
The plasma clearance of fondaparinux decreases with the severity of renal impairment, and is associated with an increased risk of hemorrhage (see ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency). This has also been observed with all low molecular weight heparins (LMWH).
In patients with severe renal impairment, i.e., creatinine clearance (CrCl) < 30 mL/min, use of Fondaparinux Sodium Injection should generally be avoided, due to increased risk of bleeding (see DOSAGE AND ADMINISTRATION, Use in Patients with Renal Insufficiency).
Prophylaxis of VTE following orthopedic or abdominal surgery
Occurrences of major bleeding in patients receiving prophylactic therapy following orthopedic surgery with normal renal function, mild renal insufficiency, moderate renal insufficiency and severe renal insufficiency have been found to be 1.6% (25/1565), 2.4% (31/1288), 3.8% (19/504) and 4.8% (4/83) respectively.
Major bleeding in patients receiving prophylactic therapy in abdominal surgery in an active- controlled trial with dalteparin sodium, occurred in 2.1% (13/606) of patients with normal renal function, in 3.6% (22/613) with mild renal impairment, in 6.7% (12/179) with moderate renal impairment, and in 7.1% (1/14) with severe renal impairment.
Therefore, Fondaparinux Sodium Injection prophylactic therapy following orthopedic or abdominal surgery is not recommended in patients with severe renal insufficiency (CrCl < 30 mL/min) and should be used with caution in patients with moderate renal insufficiency (CrCl 30-50 mL/min) (see ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency).
Renal function should be assessed periodically in orthopedic and abdominal surgery patients receiving prophylactic therapy. Consideration of immediate discontinuation of Fondaparinux Sodium Injection should be undertaken for patients who develop severe renal insufficiency or labile renal function while on prophylactic therapy. After discontinuation of Fondaparinux Sodium Injection prophylactic therapy, its anticoagulant effects may persist for 2-4 days in patients with normal renal function (i.e. at least 3-5 half-lives). The anticoagulant effects of Fondaparinux Sodium Injection prophylactic therapy may persist even longer in patients with renal insufficiency.
Treatment of DVT and PE
No dosing adjustment is generally necessary in patients with mild to moderate renal insufficiency, however, close monitoring of these patients is recommended. In patients with severe renal impairment (creatinine clearance ≤ 30 mL/min) use is not recommended due to risk of hemorrhage.
Management of UA/NSTEMI, STEMI
There are limited clinical data available on the use of fondaparinux 2.5 mg once daily in patients with creatinine clearance ≤ 30 mL/min (see DOSAGE AND ADMINISTRATION, and ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency).
6.1 Special Populations Low Body Weight
Patients with body weight < 50 kg are at increased risk of bleeding due to reduced clearance of fondaparinux sodium.
Prophylaxis of VTE following orthopedic or abdominal surgery
Fondaparinux Sodium Injection prophylactic therapy should be used with caution in patients with body weight < 50 kg undergoing orthopedic surgery.
Treatment of DVT and PE
For DVT and PE treatment, in patients with body weight < 50 kg, a daily dose of 5 mg is recommended. In patients with body weight > 100 kg, a daily dose of 10 mg is recommended (see DOSAGE AND ADMINISTRATION).
Management of UA/NSTEMI, STEMI
Fondaparinux Sodium Injection should be used with caution in patients weighing < 50 kg.
6.1.1 Pregnant Women
There are very limited clinical data available on the use of fondaparinux sodium in pregnant women. Caution should be exercised when prescribing Fondaparinux Sodium Injection to pregnant women. Fondaparinux Sodium Injection should not be prescribed to pregnant women unless the potential benefit outweighs the risk. Animal studies do not indicate either direct or indirect harmful effects with respect to pregnancy, embryonal/fetal development, parturition or post-natal development (see TOXICOLOGY).
6.1.2 Breast-feeding
Although it is not known whether fondaparinux is excreted in human milk, it has been shown to be excreted in the milk of lactating rat dams. Because many drugs may be excreted in human milk, breast feeding is not recommended during treatment with Fondaparinux Sodium Injection.
6.1.3 Pediatrics
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
6.1.4 Geriatrics
Geriatrics (> 65 years of age): Fondaparinux Sodium Injection should be used with caution in elderly patients because of increased risk of hemorrhage (see ADVERSE REACTIONS). Since fondaparinux sodium is substantially excreted by the kidney, risks associated with its use may be expected to be greater in patients with impaired renal function, including the elderly (see ADVERSE REACTIONS, and DOSAGE AND ADMINISTRATION). Because elderly patients are more likely to have decreased renal function, renal function should be monitored, as clinically warranted (see WARNINGS AND PRECAUTIONS, Renal).
7 ADVERSE REACTIONS
7.1 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The data described below reflect experience in over 25,000 patients randomized to fondaparinux sodium injection in controlled trials of hip fracture, hip replacement, major knee, or abdominal surgeries, treatment of DVT and PE, and the management of UA/NSTEMI and STEMI. Patients received fondaparinux sodium primarily in two large peri-operative dose-response trials (n=989), four active-controlled peri-operative VTE prophylaxis trials with enoxaparin sodium (n=3,616), an extended VTE prophylaxis trial (n=327), an active-controlled VTE prophylaxis trial with dalteparin sodium (n=1,425) in abdominal surgery, a dose-response trial (n=111) and an active-controlled trial with enoxaparin sodium in DVT treatment (n=1,091), an active- controlled trial with heparin in PE treatment (n=1,092), an active-controlled trial (OASIS 5) with enoxaparin in the treatment of UA/NSTEMI (n=9,979), and an active and placebo-controlled trial (OASIS 6) with standard of care in the treatment of STEMI (n=5,954), (see CLINICAL TRIALS).
Additionally, safety data were obtained from the FUTURA/OASIS 8 trial, comparing two adjunctive UFH regimens during non-primary PCI in UA/NSTEMI patients treated with fondaparinux sodium (n=2,026).
Hemorrhage
As with any antithrombotic treatment, hemorrhagic manifestations can occur. In clinical trials or in post-marketing experience, rare cases of intracranial/ intracerebral or retroperitoneal bleedings have been reported.
Prophylaxis of VTE following orthopedic surgery
The rates of major bleeding events reported during the orthopedic surgery clinical trials with fondaparinux sodium 2.5 mg injection are provided in Table 1, Table 2 and Table 3 below.
Table 1 Summary of Bleeding Results From First Injection Up to Day 11 – Percentage of Patients
| Surgery Type | Bleeding | Fondaparinux sodium 2.5 mg daily (%) | Enoxaparin (%) | |
| Hip Fracture | Major bleeding1 | 18/831 (2.2) | 19/842 (2.3) | |
| Minor bleeding2 | 34/831 (4.1) | 18/842 (2.1) | ||
| Knee Replacement | Major bleeding | 11/517 (2.15) | 1/517 (0.2) | |
| Minor bleeding | 14/517 (2.7) | 19/517 (3.7) | ||
| Hip Replacement | Study 14 | Major bleeding | 20/1128 (1.8) | 11/1129 (1.0) |
| Minor bleeding | 17/1128 (1.5) | 24/1129 (2.1) | ||
| Study 23 | Major bleeding | 47/1140 (4.1) | 32/1133 (2.8) | |
| Minor bleeding | 44/1140 (3.9) | 38/1133 (3.4) | ||
1 Major bleeding was defined as clinically overt bleeding that was (1) fatal, (2) at a critical site
(e.g. Intracranial, retroperitoneal, intra-ocular, pericardial, spinal or into adrenal gland), (3) associated with re-operation or (4) Bleeding Index (BI) ≥ 2 i.e. BI = drop in hemoglobin (Hb) pre-bleed minus post-bleed + number of units transfused. There were no fatal bleeds or bleeds at a critical site in the fondaparinux sodium group, and one fatal bleed and one bleed into a critical site in the enoxaparin group.
- 2 Minor bleeding was clinically overt bleeding that was not major.
- 3 Comparator was Enoxaparin 40 mg o.d.
- 4 Comparator was Enoxaparin 30 mg b.i.d.
- 5 p-value versus enoxaparin is 0.0081.
Table 2 Bleeding Across Hip Fracture, Hip Replacement and Knee Replacement Surgery Studies
Fondaparinux sodium 2.5 mg SC once daily | Comparator: Enoxaparin Sodium1 | |
| N = 3616 | N = 3956 | |
| Major bleeding2 | 96 (2.7%) | 75 (1.9%) |
| Fatal bleeding | 0 (0.0%) | 1 (< 0.1%) |
| Non-fatal bleeding at critical site | 0 (0.0%) | 1 (< 0.1%) |
| Re-operation due to bleeding | 12 (0.3%) | 10 (0.3%) |
| Bleeding Index (BI) ≥ 23,5 | 84 (2.3%) | 63 (1.6%) |
| Minor bleeding4 | 109 (3.0%) | 116 (2.9%) |
1 Enoxaparin Sodium dosing regimen: 30 mg every 12 hours or 40 mg once daily (see
Clinical Trials).
- 2 Major bleeding was defined as clinically overt bleeding that was (1) fatal, (2) bleeding at critical site (e.g. intracranial, retroperitoneal, intra-ocular, pericardial, spinal or into adrenal gland), (3) associated with reoperation at operative site, or (4) with a bleeding index (BI) ≥ 2.
- 3 BI ≥ 2: overt bleeding associated only with a bleeding index ≥ 2 [calculated as number of whole blood or packed red blood cells units transfused + [(pre-bleeding) - (post-bleeding)] hemoglobin (g/dL) values].
- 4 Minor bleeding was defined as clinically overt bleeding that was not major.
- 5 Incidence of BI ≥ 2 with fondaparinux sodium across the 4 phase III studies decreased when the first dose was given ≥ 6 hours after surgical closure.
Table 3 Number (Percentage) of Patients With Adjudicated Bleeding Events in Hip Fracture Surgery
| Pre-randomization Open-Label Period (Day 1 to Day 7 ± 1 post-surgery) | Randomized Double-Blind Extended Prophylaxis Period (Day 8 to Day 28 ± 2 post- surgery) | |||||||
Fondaparinux sodium N = 737 | Fondaparinux sodium N = 327 | Placebo N = 329 | ||||||
| Any bleeding | 37 (5.0%) | 13 (4.0%) | 4 (1.2%) | |||||
| Minor bleeding only1 | 15 (2.0%) | 5 (1.5%) | 2 (0.6%) | |||||
| Any major bleeding2 | 22 (3.0%) | 8 (2.4%) | 2 (0.6%) | |||||
| Fatal bleeding | 2 (0.3%) | 0 (0.0%) | 0 (0.0%) | |||||
| Non-fatal bleeding | 1 (0.1%) | 0 (0.0%) | 0 (0.0%) | |||||
| Other non-fatal major bleeding | 19 (2.6%) | 8 (2.4%) | 2 (0.6%) | |||||
| At surgical site leading to re-operation | 3 (0.4%) | 2 (0.6%) | 2 (0.6%) | |||||
Only bleeding index (BI) ≥ 23 | 16 (2.2%) | 6 (1.8%) | 0 (0.0%) | |||||
- 1 Minor bleeding was defined as clinically overt bleeding that was not major.
- 2 Major bleeding was defined as clinically overt bleeding that was (1) fatal, (2) bleeding at critical site (e.g. intracranial, retroperitoneal, intra-ocular, pericardial, spinal or into adrenal gland), (3) associated with reoperation at operative site, or (4) with a bleeding index (BI) ≥ 2.
- 3 Adjudicated as major and with BI ≥ 2 and/or decrease of hemoglobin ≥ 2 g/dL and/or number of units transfused ≥ 2.
Major bleeding from the first active fondaparinux sodium dose decreased by 26% if the first dose was given 6 hours after surgical closure: major bleeding with fondaparinux sodium started < 6 hours after surgical closure was 2.6% (n=1,337) versus major bleeding with fondaparinux sodium started 6 hours after surgical closure which was 1.9% (n=2,230).
Geriatrics: Over 2,300 patients, 65 years and older, have received fondaparinux sodium 2.5 mg in randomized clinical trials in the orthopedic surgery program. In the peri-operative, orthopedic surgery, clinical trials with patients receiving fondaparinux sodium 2.5 mg, the risk of fondaparinux sodium- associated non-fatal major bleeding increased with age: 1.8% (23/1,253) in patients < 65 years, 2.2% (24/1,111) in those 65-74 years, and 2.7% (33/1,227) in those ≥ 75 years. Serious adverse events increased with age for patients receiving fondaparinux sodium. In patients undergoing extended prophylaxis following the first week of therapy, the incidence of fondaparinux sodium-associated non- fatal major bleeding was: 1.9% (1/52) in patients < 65 years, 1.4% (1/71) in those 65-74 years, and 2.9% (6/204) in those ≥ 75 years.
Prophylaxis of VTE following abdominal surgery
The rates of major bleeding reported during an abdominal surgery clinical trial with fondaparinux sodium 2.5 mg are provided in Table 4 below.
Table 4 Major and Non-Major Bleeding Episodes1 in a Randomized, Controlled, Abdominal Surgery Study
| Study 1 | |||||
Fondaparinux sodium 2.5 mg SC once daily | Dalteparin Sodium 5,000 IU SC once daily | ||||
| N = 1433 | N = 1425 | ||||
| Major bleeding1 | 49 (3.4%) | 34 (2.4%) | |||
| Fatal bleeding | 2 (0.1%) | 2 (0.1%) | |||
| Non-fatal bleeding at critical site | 0 (0.0%) | 0 (0.0%) | |||
Other non-fatal major bleeding Surgical site Non-surgical site | 38 (2.7%) 9 (0.6%) | 26 (1.8%) 6 (0.4%) | |||
| Minor bleeding2 | 31 (2.2%) | 23 (1.6%) | |||
1 Major bleeding was defined as bleeding that was (1) fatal, (2) bleeding at the surgical site leading to intervention,
(3) non-surgical bleeding at a critical site (eg. intracranial, retroperitoneal, intra-ocular, pericardial, spinal, or into adrenal gland), or leading to an intervention, and/or with a bleeding index (BI ≥2 calculated as [number of whole blood or packed red blood cell unites transfused + [(pre-bleeding) – (post-bleeding)] hemoglobin (g/dL) values]).
- 2 Minor bleeding was defined as clinically overt bleeding that was not major.
Geriatrics: In the abdominal surgery active-controlled clinical trial with dalteparin sodium, the risk of major bleeding associated with use of fondaparinux sodium increased with age: 3.0% (19/644) in patients < 65 years, 3.2% (16/507) in those 65-74 years, and 5.0% (14/282) in those ≥ 75 years.
Treatment of DVT and PE
The rates of major bleeding events reported during the DVT and PE clinical trials with the fondaparinux sodium injection treatment regimen are provided in Table 5 below.
Table 5 Major Bleeding Episodes1,2 in DVT and PE Treatment Studies
Indications
Fondaparinux sodium Treatment Regimen | Enoxaparin Sodium1 mg/kg SC q 12h | Heparin IV aPTT adjusted | |
| N = 2294 | N = 1101 | N = 1092 | |
| DVT and PE Treatment | 28 (1.2%) | 13 (1.2%) | 12 (1.1%) |
1 Major bleeding was defined as clinically overt - and/or contributing to death - and/or in a
critical organ including intracranial, retroperitoneal, intraocular, spinal, pericardial or adrenal gland - and/or associated with a fall in hemoglobin level = 2 g/dL - and/or leading to a transfusion ≥ 2 units of packed red blood cells or whole blood.
- 2 Bleeding rates are during the study drug treatment period (approximately 7 days). Patients were also treated with vitamin K antagonists initiated within 72 hours after the first study drug administration.
Geriatrics: Over 1,200 patients, 65 years and older, have received the fondaparinux sodium treatment regimen in the DVT and PE treatment clinical trials. In the DVT and PE treatment clinical trials with patients receiving the fondaparinux sodium treatment regimen, the risk of fondaparinux sodium-associated non-fatal major bleeding increased with age: 0.6% (7/1,151) in patients < 65 years, 1.6% (9/560) in those 65-74 years, and 2.1% (12/583) in those ≥ 75 years. Careful attention to dosing directions and concomitant medications (especially antiplatelet medication) is advised (see DRUG INTERACTIONS).
Management of UA/NSTEMI
The rates of major bleeding events reported during the management of UA/NSTEMI clinical trials with fondaparinux sodium 2.5 mg injection are provided in Table 6 and Table 7 below.
Table 6 Bleeding Episodes in OASIS 5, a Randomized, Controlled Study in UA/NSTEMI5
| Up to 9 days after presenting with UA/NSTEMI | ||||||
Fondaparinux sodium 5 N = 9979 | Enoxaparin6 N = 9969 | |||||
| Investigator Reported Major Bleeding1 | 205 (2.1%) | 410 (4.1%) | ||||
| Fatal bleeding | 7 (<0.1%) | 22 (0.2%) | ||||
| Intracranial | 7 (<0.1%) | 7 (<0.1%) | ||||
| Retroperitoneal | 9 (<0.1%) | 36 (0.4%) | ||||
| Requiring surgical intervention | 39 (0.4%) | 78 (0.8%) | ||||
| Drop in hemoglobin ≥ 3 g/dL | 189 (1.9%) | 385 (3.9%) | ||||
| Blood transfusion ≥ 2 units | 156 (1.6%) | 280 (2.8%) | ||||
| Modified TIMI Severe Hemorrhage2 | 148 (1.5%) | 260 (2.6%) | ||||
| Minor Bleeding3 | 115 (1.2%) | 320 (3.2%) | ||||
| PCI-related bleed4 | 82 (0.8%) | 183 (1.8%) | ||||
| CABG-related bleed4 | 86 (0.9%) | 72 (0.7%) | ||||
- 1 Major bleeding was defined as clinically overt bleeding with at least one of the following criteria: fatal, symptomatic intracranial hemorrhage, retroperitoneal hemorrhage, intraocular hemorrhage leading to significant vision loss, bleeding requiring surgical intervention, decrease in Hb of ≥ 3 g/dL, or blood transfusion ≥ 2 units.
2 Modified TIMI severe hemorrhage was defined as fatal hemorrhage, intracranial hemorrhage, cardiac
tamponade, or a clinically significant hemorrhage with a decrease in Hb of > 5 g/dL.
- 3 Minor bleeding was defined as clinically overt bleeding that was not major and that led to interruption of study drug for at least 24 hours, or transfusion of one unit of blood.
- 4 The number of patients undergoing PCI was 3,422 for fondaparinux sodium and 3,410 for enoxaparin and the number of patients undergoing CABG was 956 for fondaparinux sodium and 886 for enoxaparin.
- 5 Patients randomized to fondaparinux sodium received 2.5 mg fondaparinux SC once daily for up to 8 days or discharge.
- 6 Patients randomized to enoxaparin sodium received 1 mg/kg enoxaparin SC twice daily (once daily if creatinine clearance was between 20 mL/min and 30 mL/min) for 2-8 days or until clinically stable.
Table 7 Incidence of Adjudicated Major Bleeding in OASIS 5 at Day 9 in UA/NSTEMI Patients Treated with Fondaparinux sodium by Renal Function Status at Baseline
Covariate Endpoint/ Timepoint | Number Events / Number Analyzed | OR/HR1 (95% CI) | Interaction p-value4 | ||||||||
| Fondaparinux sodium 2 | Enoxaparin 3 | ||||||||||
| On therapy | 183/9943 (1.8%) | 388/9928 (3.9%) | 0.46 (0.38, 0.55) | 0.343 | |||||||
| <20 mL/min | 1/40 (2.5%) | 5/43 (11.6%) | 0.19 (0.02, 1.75) | ||||||||
| ≥20 - <30 mL/min | 4/240 (1.7%) | 19/239 (7.9%) | 0.20 (0.07, 0.59) | ||||||||
| ≥30 - <50 mL/min | 47/1649 (2.9%) | 104/1715 (6.1%) | 0.45 (0.32, 0.65) | ||||||||
| ≥50 - <80 mL/min | 93/4,257 (2.2%) | 185/4,188 (4.4%) | 0.48 (0.38, 0.62) | ||||||||
| ≥80 mL/min | 38/3,757 (1.0%) | 75/3,743 (2.0%) | 0.50 (0.34, 0.74) | ||||||||
Creatinine clearance not recorded | 0/36 | 1/41 (2.4%) | |||||||||
| Day 9 | 209/9979 (2.1%) | 405/9969 (4.1%) | 0.51 (0.43, 0.60) | 0.248 | |||||||
| <20 mL/min | 2/40 (5.0%) | 5/43 (11.6%) | 0.41 (0.08, 2.11) | ||||||||
| ≥20 - <30 mL/min | 4/240 (1.7%) | 21/239 (8.8%) | 0.19 (0.06, 0.54) | ||||||||
| ≥30 - <50 mL/min | 54/1649 (3.3%) | 107/1715 (6.2%) | 0.52 (0.37, 0.71) | ||||||||
| ≥50 - <80 mL/min | 103/4257 (2.4%) | 193/4188 (4.6%) | 0.52 (0.41, 0.66) | ||||||||
| ≥80 mL/min | 46/3757 (1.2%) | 79/3743 (2.1%) | 0.58 (0.40, 0.83) | ||||||||
Creatinine clearance not recorded | 0/36 | 1/41 (2.4%) | |||||||||
Note: Creatinine clearance was included as a continuous variable in the estimate of the overall hazard/odds ratio and covariate p-value.
- 1 Odds ratio for the on-therapy analysis; hazard ratio for the Day 9 analysis.
- 2 Patients randomized to fondaparinux sodium received 2.5 mg fondaparinux SC once daily for up to 8 days or discharge.
- 3 Patients randomized to enoxaparin sodium received 1 mg/kg enoxaparin SC twice daily (once daily if creatinine clearance was between 20 mL/min and 30 mL/min) for 2-8 days or until clinically stable.
- 4 Treatment by Covariate Interaction (test for homogeneity of treatment effect).
In a study of 3,235 high-risk UA/NSTEMI patients scheduled for angiography and treated with open-label fondaparinux (FUTURA/OASIS 8), the 2,026 patients indicated for PCI were randomized to receive one of two double-blind dose regimens of adjunctive unfractionated heparin (UFH). All enrolled patients received fondaparinux 2.5 mg subcutaneously, once daily for up to 8 days, or until hospital discharge. Randomized patients received either “low dose” UFH regimen (50 U/kg irrespective of planned GPIIb/IIIa use; non ACT-guided) or “standard dose” UFH regimen (85 U/kg, ACT-guided, if no GPIIb/IIIa use; or 60 U/kg, ACT-guided, if planned GPIIb/IIIa use), immediately prior to the start of the PCI.
The primary endpoint was a composite of peri-PCI (defined as time of randomization up to 48 hours post-PCI) adjudicated major or minor bleeding, or non-adjudicated major vascular access site complications. It is noteworthy that FUTURA/OASIS 8 was underpowered to conclusively rule out any statistically significant differences between both UFH groups.
Table 8 Incidence of Peri-PCI Major or Minor Bleeding, or Major Vascular Access Site Complications, in High-Risk UA/NSTEMI Patients in FUTURA/OASIS 8 Receiving Fondaparinux sodium With Either Low-Dose or Standard Dose5 Adjunctive UFH during PCI
| Endpoints, n (% ) | Incidence | Odds Ratio1 (95%CI) | p- value | ||||||
Low-Dose UFH N = 1,024 | Standard Dose UFH N = 1,002 | ||||||||
Primary Peri-PCI major 2or minor3 bleeding, or major vascular access site complications4 | 48 (4.7%) | 58 (5.8%) | 0.80 (0.54, 1.19) | 0.267 | |||||
| Secondary | 14 (1.4%) | 12 (1.2%) | 1.14 (0.53, 2.49) | 0.734 | |||||
| Peri-PCI major bleeding | |||||||||
| Peri-PCI minor bleeding | 7 (0.7%) | 17 (1.7%) | 0.40 (0.16, 0.97) | 0.042 | |||||
| Major vascular access site | 33 (3.2%) | 43 (4.3%) | 0.74 (0.47, 1.18) | 0.207 | |||||
| complications | |||||||||
| Peri-PCI major bleeding, or death, | 59 (5.8%) | 39 (3.9%) | 1.51 (1.00, 2.28) | 0.051 | |||||
| MI or TVR up to Day 30. | |||||||||
| Death, MI or TVR up to Day 30. | 46 (4.5%) | 29 (2.9%) | 1.58 (0.98, 2.53) | 0.059 | |||||
| Death up to Day 30 | 8 (0.8%) | 6 (0.6%) | 1.31 (0.45, 3.78) | 0.621 | |||||
| MI up to Day 30 | 31 (3.0%) | 25 (2.5%) | 1.22 (0.72, 2.08) | 0.466 | |||||
| TVR up to Day 30 | 9 (0.9%) | 3 (0.3%) | 2.95 (0.80, 10.93) | 0.105 | |||||
TVR, Target Vessel Revascularisation; MI, Myocardial Infarction
- 1 Odds ratio: Low Dose/Standard Dose
- 2 Major bleeding was defined as clinically overt bleeding with at least one of the following criteria: fatal, symptomatic intracranial hemorrhage, retroperitoneal hemorrhage, intraocular hemorrhage leading to significant vision loss, bleeding requiring surgical intervention, decrease in Hb of ≥ 3 g/dL, or blood transfusion ≥ 2 units. Peri-PCI includes the time of randomization up to 48 hours post-PCI.
- 3 Minor bleeding was defined as clinically overt bleeding that was not major and that led to interruption of study drug for at least 24 hours, or transfusion of one unit of blood.
- 4 Major vascular access site complications include large hematoma, pseudoaneurysm requiring treatment, arteriovenous fistula, or other vascular procedures related to the access site.
- 5 For description of low-dose or standard dose, see narrative text, two paragraphs above this Table
Risk of catheter thrombosis during PCI
Clinical trials have shown an increased risk of guiding catheter thrombosis in patients treated solely with fondaparinux sodium for anticoagulation during percutaneous coronary intervention (PCI) compared to control (see WARNINGS AND PRECAUTIONS, Cardiovascular). The incidence of catheter thrombosis in UA/NSTEMI patients undergoing PCI in OASIS 5 were 0.9% (29/3173) with fondaparinux sodium, 0.3% (6/1,883) with enoxaparin alone, and 0.2% (2/1,286) with enoxaparin with adjunctive UFH. In OASIS 5, patients randomized to fondaparinux sodium received fondaparinux sodium as the sole adjunctive therapy during PCI whereas enoxaparin subjects received enoxaparin with or without UFH during PCI based on the timing since the last subcutaneous injection of enoxaparin.
In fondaparinux sodium-treated high risk UA/NSTEMI patients randomized to receive low-dose or standard regimens of UFH during non-primary PCI (see FUTURA/OASIS 8 trial description above), the incidences of adjudicated catheter thrombus were 0.5% (5/1,024), and 0.1%
(1/1,002), respectively (see WARNINGS AND PRECAUTIONS, Cardiovascular). In addition, in non-randomized patients, four (0.3%) cases of confirmed catheter thrombus occurred during diagnostic angiography. Of the 3,235 patients enrolled in the trial, thirteen (0.40%) in total experienced thrombus in the arterial sheath, with 7 cases of sheath thrombosis during angiography and 6 during PCI.
Fondaparinux Sodium Injection should not be used as the sole anticoagulant during PCI because of an increased risk of guiding catheter thrombosis. An effective anti-thrombin regimen such as unfractionated heparin (UFH) should be administered as an adjunct to PCI according to standard practice (see WARNINGS AND PRECAUTIONS, Cardiovascular).
Geriatrics: Nearly 8,000 UA/NSTEMI patients, 65 years or older, received treatment with fondaparinux sodium in OASIS 5 and FUTURA/OASIS 8. In the OASIS-5 study, the rate of major bleeding at Day 9 was: 1.3% (50/3,885) in patients < 65 years, 2.4% (89/3,644) in those 65-74 years, and 2.9% (71/2,450) in those ≥ 75 years.
Management of STEMI
The rates of major bleeding events reported during the management of STEMI clinical trials with fondaparinux sodium 2.5 mg injection are provided in Table 9 below.
Table 9 Bleeding Episodes1,2 in OASIS 6, Randomized, Controlled Study in STEMI3
| Up to 9 days after presenting with STEMI (Number (%) Subjects) | ||||||||||||||||||||||||
| Overall | Stratum 1 | Stratum 2 | ||||||||||||||||||||||
| Investigator reported bleeding events | Fondaparinux sodium 3 N = 5954 | Control (UFH/placebo) N = 5947 | Fondaparinux sodium 3 N = 2808 | Placebo N=2818 | Fondaparinux sodium 3 N = 3146 | UFH N=3129 | ||||||||||||||||||
Modified TIMI Severe Hemorrhage1 | 78 (1.3%) | 94 (1.6%) | 34 (1.2%) | 48 (1.7%) | 44 (1.4%) | 46 (1.5%) | ||||||||||||||||||
| Fatal | 35 (0.6%) | 48 (0.8%) | 19 (0.7%) | 32 (1.1%) | 16 (0.5%) | 16 (0.5%) | ||||||||||||||||||
| Intracranial | 12 (0.2%) | 12 (0.2%) | 6 (0.2%) | 7 (0.2%) | 6 (0.2%) | 5 (0.2%) | ||||||||||||||||||
| Cardiac tamponade | 26 (0.4%) | 47 (0.8%) | 15 (0.5%) | 30 (1.1%) | 11 (0.3%) | 17 (0.5%) | ||||||||||||||||||
| Drop in Hgb ≥ 5 g/dL | 37 (0.6%) | 34 (0.6%) | 12 (0.4%) | 10 (0.4%) | 25 (0.8%) | 24 (0.8%) | ||||||||||||||||||
| By Reperfusion strategy | ||||||||||||||||||||||||
| No reperfusion | 13/1415 (0.9%) | 20/1367 (1.5%) | 3/620 (0.5%) | 5/599 (0.8%) | 10/795 (1.3%) | 15/768 (2.0%) | ||||||||||||||||||
| Thrombolytic group | 34/2676 (1.3%) | 55/2711 (2.0%) | 25/2182 (1.1%) | 41/2214 (1.9%) | 9/494 (1.8%) | 14/497 (2.8%) | ||||||||||||||||||
| Primary PCI | 17/1863 (0.9%) | 8/1869 (0.4%) | 0/6 | 0/5 | 17/1857 (0.9%) | 8/1864 (0.4%) | ||||||||||||||||||
| Major Bleeding2 | 104 (1.7%) | 131 (2.2%) | 40 (1.4%) | 61 (2.2%) | 64 (2.0%) | 70 (2.2%) | ||||||||||||||||||
| Minor Bleeding | 37 (0.6%) | 23 (0.4%) | 19 (0.7%) | 6 (0.2%) | 18 (0.6%) | 17 (0.5%) | ||||||||||||||||||
| PCI related bleeding | 45 (0.8%) | 47 (0.8%) | 7 (0.2%) | 3 (0.1%) | 38 (1.2%) | 44 (1.4%) | ||||||||||||||||||
| CABG related bleeding | 3 (<0.1%) | 6 (0.1%) | 1 (<0.1%) | 3 (0.1%) | 2 (<0.1%) | 3 (<0.1%) | ||||||||||||||||||
- 1 Severe hemorrhage was defined according to a modified TIMI criteria as: fatal hemorrhage, intracranial hemorrhage, cardiac tamponade, or a clinically significant hemorrhage with a decrease in Hb of >5 g/dL.
- 2 Major bleeding was defined as clinically overt bleeding with at least one of the following criteria: fatal, symptomatic intracranial hemorrhage, retroperitoneal hemorrhage, intraocular hemorrhage leading to significant vision loss, bleeding requiring surgical intervention, decrease in Hb of >3.0 g/dL, or blood transfusion ≥2 units.
3 Patients randomized to fondaparinux sodium received an IV bolus injection of 2.5 mg followed by 2.5 mg by SC injection daily for up to 8 days or discharge.
In those patients who underwent non-primary PCI < 6 hours after the last dose of fondaparinux, the median dose of UFH used was 5000 IU and the incidence of major bleeding was 4.1% (2/49).
In those patients who underwent non-primary PCI 6-24 hours after the last dose of fondaparinux, the median dose of UFH was 8000 IU and the incidence of major bleeding was 2% (2/98).
The relative effects of fondaparinux sodium compared to control on severe hemorrhage or any hemorrhage up to Day 9 by clopidogrel use were consistent with that observed for the overall population.
Risk of catheter thrombosis during PCI
Clinical trials have shown an increased risk of guiding catheter thrombosis in patients treated solely with fondaparinux sodium for anticoagulation during percutaneous coronary intervention (PCI) compared to control (see WARNINGS AND PRECAUTIONS, Cardiovascular). The incidence of catheter thrombus in STEMI patients undergoing primary PCI were 1.18% (22/1,862) for fondaparinux sodium, when fondaparinux sodium was used as the sole adjunctive therapy, compared to 0% for UFH (0/1,853). In STEMI patients treated with fondaparinux sodium undergoing non-primary PCI (234 patients, 238 procedures) who received UFH as an adjunct to the procedure, no cases of guiding catheter thrombus occurred.
In STEMI patients undergoing primary percutaneous coronary intervention (PCI) for reperfusion, the use of Fondaparinux Sodium Injection prior to and during PCI is not recommended (see WARNINGS AND PRECAUTIONS, Cardiovascular, and DOSAGE AND ADMINISTRATION).
Geriatrics: Over 2,300 STEMI patients, 65 years or older, received treatment with fondaparinux sodium in OASIS 6. In the STEMI clinical trials with patients receiving fondaparinux sodium, the risk of severe hemhorrage was: 0.6% (22/3,565) in patients < 65 years, 1.5% (23/1,518) in those 65-74 years, and 2.2% (19/871) in those ≥ 75 years.
Non-hemorrhagic adverse events
Other adverse events that occurred during treatment with fondaparinux sodium or enoxaparin sodium in clinical trials with patients undergoing hip fracture surgery, hip replacement surgery, or knee replacement surgery and that occurred at a rate of at least 2% in either treatment group, are provided in Table 10 and Table 11 below.
Other adverse events that occurred during treatment with fondaparinux sodium or dalteparin sodium in a clinical trial with patients undergoing abdominal surgery that occurred at a rate of at least 2% in either treatment group are provided in Table 12 below.
Table 10 Adverse Events Occurring in Greater Than or Equal to 2 Percent of Fondaparinux Sodium or Enoxaparin Sodium Treated Patients Regardless of Relationship to Study Drug Across Hip Fracture, Hip Replacement Surgery, or Knee Replacement Surgery Studies
| Adverse Events | Fondaparinux sodium 2.5 mg SC once daily N = 3616 | Comparator: Low Molecular Weight Heparin or Enoxaparin Sodium1 N = 3956 | ||
| Anemia | 19.6% | 16.9% | ||
| Fever | 13.6% | 15.4% | ||
| Nausea | 11.3% | 12.2% | ||
| Edema | 8.7% | 8.8% | ||
| Constipation | 8.5% | 10.5% | ||
| Rash | 7.5% | 8.3% | ||
| Vomiting | 5.9% | 6.0% | ||
| Insomnia | 5.0% | 5.4% | ||
| Wound drainage increased | 4.5% | 4.7% | ||
| Hypokalemia | 4.2% | 4.1% | ||
| Urinary tract infection | 3.8% | 3.4% | ||
| Dizziness | 3.6% | 4.2% | ||
| Purpura | 3.5% | 3.5% | ||
| Hypotension | 3.5% | 3.2% | ||
| Confusion | 3.1% | 3.3% | ||
| Bullous eruption | 3.1% | 2.6% | ||
| Urinary retention | 2.9% | 3.0% | ||
| Hematoma | 2.8% | 2.8% | ||
| Diarrhea | 2.5% | 2.6% | ||
| Dyspepsia | 2.4% | 2.6% | ||
| Post-operative hemorrhage | 2.4% | 1.7% | ||
| Headache | 2.0% | 2.5% | ||
| Pain | 1.7% | 2.6% | ||
| 1 Enoxaparin Sodium dosing regimen: 30 mg every 12 hours or 40 mg once daily. | ||||
Table 11 Adverse Events Occurring in Greater Than or Equal to 2 Percent of Fondaparinux Sodium or Placebo Treated Patients Regardless of Relationship to Study Drug During Pre-randomization Open Label Period and Extended Prophylaxis period After Hip Fracture Surgery
| Pre-randomization Open-Label Period (Day 1 to Day 7 ± 1 post-surgery) | Randomized Double-Blind Extended Prophylaxis Period (Day 8 to Day 28 ± 2 post- surgery) | ||||||
| Adverse Events | Fondaparinux sodium N = 737 | Fondaparinux sodium N =327 | Placebo SC N = 329 | ||||
| Constipation | 7.1% | 1.8% | 2.1% | ||||
| Anemia | 5.8% | 1.5% | 1.2% | ||||
| Nausea | 4.6% | 0.3% | 1.2% | ||||
| Confusion | 4.1% | 1.2% | 0.3% | ||||
| Fever | 4.1% | 0.3% | 1.2% | ||||
| Urinary tract infection | 3.1% | 4.0% | 4.0% | ||||
| Vomiting | 2.7% | 0.6% | 1.2% | ||||
| Post-operative hemorrhage | 2.4% | 0.6% | 0.6% | ||||
| Hematoma | 1.2% | 2.1% | 0.3% | ||||
| Surgical site reaction | 0.7% | 1.5% | 2.4% | ||||
| Diarrhea | 0.5% | 1.8% | 2.4% | ||||
Table 12 Adverse Events Occurring in Greater Than or Equal to 2 Percent of Patients Treated With Fondaparinux Sodium or Dalteparin Sodium Undergoing Abdominal Surgery Regardless of Relationship to Study Drug
| Adverse Events | Fondaparinux sodium 2.5 mg SC once daily N = 1433 | Dalteparin Sodium 5000 IU SC once daily N = 1425 |
| Post-operative wound infection | 4.9% | 4.8% |
| Post-operative haemorrhage | 4.3% | 2.9% |
| Fever | 3.7% | 3.8% |
| Surgical site reaction | 3.2% | 2.8% |
| Anaemia | 2.4% | 1.8% |
| Hypertension | 2.4% | 2.9% |
| PNEUMONIA | 2.3% | 1.6% |
| VOMITING | 2.2% | 1.8% |
Other adverse events that occurred during treatment with fondaparinux sodium, enoxaparin sodium or heparin in the DVT and PE treatment clinical trials and that occurred at a rate of at least 2% in any treatment group are provided in Table 13 below.
Table 13 Adverse Events Occurring in Greater Than or Equal to 2 Percent of Fondaparinux Sodium or Enoxaparin Sodium or Heparin Treated Patients Regardless of Relationship to Study Drug Across VTE Treatment Studies
Adverse Events
Fondaparinux sodium Treatment Regimen | Enoxaparin Sodium 1 mg/kg SC q 12h | Heparin IV aPTT adjusted | |
| N = 2294 | N = 1101 | N = 1092 | |
| Constipation | 106 (4.6%) | 32 (2.9%) | 93 (8.5%) |
| Headache | 104 (4.5%) | 37 (3.4%) | 65 (6.0%) |
| Insomnia | 86 (3.7%) | 19 (1.7%) | 75 (6.9%) |
| Fever | 81 (3.5%) | 32 (2.9%) | 47 (4.3%) |
| Nausea | 76 (3.3%) | 29 (2.6%) | 53 (4.9%) |
| Urinary Tract Infection | 53 (2.3%) | 20 (1.8%) | 24 (2.2%) |
| Coughing | 48 (2.1%) | 7 (0.6%) | 26 (2.4%) |
| Diarrhea | 43 (1.9%) | 22 (2.0%) | 27 (2.5%) |
| Abdominal Pain | 33 (1.4%) | 14 (1.3%) | 28 (2.6%) |
| Chest Pain | 33 (1.4%) | 8 (0.7%) | 26 (2.4%) |
| Leg Pain | 31 (1.4%) | 10 (0.9%) | 22 (2.0%) |
| Back Pain | 30 (1.3%) | 11 (1.0%) | 34 (3.1%) |
| Epistaxis | 30 (1.3%) | 12 (1.1%) | 41 (3.8%) |
| Prothrombin decreased | 30 (1.3%) | 3 (0.3%) | 34 (3.1%) |
| Anemia | 28 (1.2%) | 3 (0.3%) | 23 (2.1%) |
| Vomiting | 26 (1.1%) | 14 (1.3%) | 27 (2.5%) |
| Hypokalemia | 25 (1.1%) | 2 (0.2%) | 23 (2.1%) |
| Bruise | 24 (1.0%) | 24 (2.2%) | 14 (1.3%) |
| Anxiety | 18 (0.8%) | 8 (0.7%) | 22 (2.0%) |
| Hepatic Function abnormal | 10 (0.4%) | 14 (1.3%) | 24 (2.2%) |
| Hepatic Enzymes increased | 7 (0.3%) | 52 (4.7%) | 30 (2.7%) |
| ALT increased | 7 (0.3%) | 47 (4.3%) | 8 (0.7%) |
| AST increased | 4 (0.2%) | 31 (2.8%) | 3 (0.3%) |
Other adverse events that occurred during treatment with fondaparinux sodium, enoxaparin, UFH or placebo in clinical trials with acute coronary syndrome patients and that occurred at a rate of at least 2% in any treatment group, are described in Table 14 below.
Table 14 Adverse Events Occurring in ≥ 2 % of Fondaparinux sodium or Control1 Treated Patients Regardless of Relationship to Study Drug Across Studies of UA/NSTEMI (OASIS 5) and STEMI (OASIS 6)
| Number (%) Subjects | ||||||||||||||||||||||||
| OASIS 5 | OASIS 6 | |||||||||||||||||||||||
| Overall | Stratum 1 | Stratum 2 | ||||||||||||||||||||||
Fondaparinux sodium N=9979 | Enoxaparin N=9969 | Fondaparinux sodium N=5954 | Control1 N=5947 | Fondaparinux sodium N=2808 | Placebo N=2818 | Fondaparinux sodium N=3146 | UFH N=3129 | |||||||||||||||||
| Any AE2 | 2426 (24) | 2785 (28) | 1933 (32) | 1959 (33) | 922 (33) | 954 (34) | 1011 (32) | 1005 (32) | ||||||||||||||||
| Headache | 227 (2) | 226 (2) | 105 (2) | 118 (2) | 60 (2) | 63 (2) | 45 (1) | 55 (2) | ||||||||||||||||
Atrial fibrillation | 103 (1) | 124 (1) | 164 (3) | 126 (2) | 69 (2) | 57 (2) | 95 (3) | 69 (2) | ||||||||||||||||
| Pyrexia | 96 (<1) | 110 (1) | 189 (3) | 200 (3) | 119 (4) | 125 (4) | 70 (2) | 75 (2) | ||||||||||||||||
| Chest pain | 148 (1) | 147 (1) | 108 (2) | 79 (1) | 50 (2) | 42 (1) | 58 (2) | 37 (1) | ||||||||||||||||
| Vomiting | 50 (<1) | 62 (<1) | 74 (1) | 74 (1) | 47 (2) | 42 (1) | 27 (1) | 32 (1) | ||||||||||||||||
Ventricular tachycardia | 35 (<1) | 28 (<1) | 76 (1) | 81 (1) | 26 (<1) | 29 (1) | 50 (2) | 52 (2) | ||||||||||||||||
- 1 OASIS 5 is a study in UA/NSTEMI and OASIS 6 is a study in STEMI. Control for the OASIS 5 study was enoxaparin and for the OASIS 6 study was placebo or UFH.
2 Includes any efficacy outcomes (except hemorrhagic stroke), non-fatal cardiac arrest and heart failure reported as AEs by the investigator in contravention of the protocol.
Other adverse events reported in greater than or equal to 1% of high-risk UA/NSTEMI patients treated with fondaparinux sodium and receiving either “low-dose” or “standard dose” of adjunctive intravenous UFH during non-primary PCI in FUTURA/OASIS 8, included headache, pyrexia, post-procedural discharge, hypotension, cough and dizziness. No individual AE occurred in greater than 3% of subjects. For those high-risk UA/NSTEMI patients in the same trial, who were not indicated for PCI and were treated with fondaparinux sodium only, the other adverse events occurring in greater than or equal to 1% of patients, included headache (1.5%), gastritis (1.2%), urinary tract infection (1.2%), asthenia (1.1%) and pyrexia (1.1%).
Thrombocytopenia: See WARNINGS AND PRECAUTIONS, Hematologic,
Thrombocytopenia.
Liver Function Tests
Prophylaxis of VTE following orthopedic surgery
Transient elevation of liver transaminases (AST and ALT) to > 3 times the upper limit of laboratory range have been observed with the peri-operative prophylactic use of fondaparinux sodium as have been seen with other antithrombotics such as low molecular weight heparins. Such elevations are fully reversible and are rarely associated with increases in bilirubin. Transient transaminase increases > 3 times upper limit of laboratory range during the extended prophylaxis clinical trial were as follows: ALT - 4 /272 (1.5%) fondaparinux sodium vs. 2 /274 (0.7%) placebo; AST- 2 /268 (0.7%) fondaparinux sodium vs. 1/ 271 (0.4%) placebo. However, these increases were reversible and there was no significant difference in the change in the hepatic enzymes between the two treatment groups from the baseline post-randomization period to the last value on double blind treatment.
Treatment of DVT and PE
In the DVT and PE treatment clinical trials asymptomatic increases in AST and ALT levels > 3 times the upper limit of normal of the laboratory reference range have been reported in 0.7% and 1.3% of patients, respectively, during the fondaparinux sodium treatment regimen.
In comparison, these increases have been reported in 4.8% and 12.3% of patients, respectively, in the DVT treatment trial during treatment with enoxaparin sodium 1 mg/kg every 12 hours, and in 2.9% and 8.7% of patients, respectively, in the PE treatment trial during treatment with aPTT adjusted heparin.
Allergic Reaction
Skin rash and allergic reactions have been observed with fondaparinux sodium use, but are uncommon. As with any subcutaneous injection, mild local irritation (injection site bleeding, rash and pruritis) may occur following subcutaneous injection of Fondaparinux Sodium Injection.
Very rare reports of angioedema and anaphylactoid/anaphylactic reactions (< 0.01%) have been received.
Other Adverse Reactions
Other adverse reactions that occurred during treatment with fondaparinux sodium in clinical trials with patients undergoing hip fracture surgery, hip replacement surgery, knee replacement surgery or abdominal surgery and that occurred at a rate of less than 1.0%, include the following: thrombocytopenia, thrombocythemia, abnormal platelets, and coagulation disorder. Adverse reactions events that have occurred at a rate of less than 0.1% in patients during clinical trials include: somnolence, vertigo, dyspnea, fatigue, flushing, and syncope.
7.2 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of fondaparinux sodium. Rare spontaneous reports of elevated aPTT have been received at the 2.5 mg dose. A causal association between treatment with fondaparinux and the occurrence of elevated aPTT has not been established.
8 DRUG INTERACTIONS
- 8.1 Drug-Drug Interactions
In clinical studies performed with fondaparinux sodium, the concomitant use of oral anticoagulants (warfarin), platelet inhibitors (acetylsalicylic acid), NSAIDs (piroxicam) and digoxin did not interact with the pharmacokinetics/pharmacodynamics of fondaparinux sodium. In addition, fondaparinux sodium neither influenced the pharmacodynamics of warfarin, acetylsalicylic acid, piroxicam and digoxin, nor the pharmacokinetics of digoxin at steady state.
Agents that may enhance the risk of hemorrhage should be discontinued prior to initiation of Fondaparinux Sodium Injection therapy unless indicated for the management of the underlying condition, such as vitamin K antagonists for the treatment of venous thromboembolism (VTE). If co-administration is necessary, close monitoring may be appropriate.
Since fondaparinux does not inhibit isozymes of the CYP P450 system in vitro (CYP 1A2, CYP 2A6, CYP 2C9, CYP 2C19, CYP 2D6, CYP 2E1 or CYP 3A4), Fondaparinux Sodium Injection is not expected to interact with other drugs metabolized in vivo via these isozymes.
Fondaparinux sodium does not bind significantly to plasma proteins other than ATIII, therefore, drug interactions by protein binding displacement are not expected.
8.2 Drug-Food Interactions
Interactions with food have not been established.
8.3 Drug-Herb Interactions
Interactions with herbal products have not been established.
8.4 Drug-Laboratory Test Interactions
See WARNINGS AND PRECAUTIONS - Monitoring, Laboratory and Coagulation Tests.
9 ACTION AND CLINICAL PHARMACOLOGY
- 9.1 Mechanism of Action
Fondaparinux sodium is a synthetic and specific inhibitor of activated Factor X (Xa). As Fondaparinux Sodium Injection has no animal-sourced components, there is no risk of animal contamination such as transmissable spongiform encephalitis (TSE).
The mechanism of action of fondaparinux sodium is the potentiation of antithrombin III (ATIII) which selectively inhibits Factor Xa. By selectively binding to ATIII, fondaparinux sodium potentiates approximately 300 times the neutralization of Factor Xa. Neutralization of Factor Xa interrupts the blood coagulation cascade and thus inhibits thrombin formation and thrombus development.
Fondaparinux sodium does not inactivate thrombin (activated Factor II) and has no effect on platelets. At the recommended dose, Fondaparinux Sodium Injection does not affect fibrinolytic activity or bleeding time.
At equivalent antithrombotic concentrations, experimental bleeding models demonstrate that fondaparinux sodium induces less bleeding than unfractionated heparin.
Fondaparinux sodium does not bind to Human Platelet Factor 4 (unlike heparin) and does not cross-react with sera from patients with heparin-induced thrombocytopenia. No thrombocytopenia with suspected immuno-allergic pathophysiology was documented in the overall clinical development program or in post-marketing experience.
Anti-Xa Activity: The pharmacodynamics/pharmacokinetics of fondaparinux sodium are derived from fondaparinux plasma concentrations quantified via anti-Factor Xa activity. Only fondaparinux can be used to calibrate the anti-Xa assay. (The international standards of heparin or Low Molecular Weight Heparin [LMWH] are not appropriate for this use). As a result, the activity of fondaparinux sodium is expressed as milligram (mg) of the fondaparinux calibrator. The anti-Xa activity of the drug increases with increasing drug concentration, reaching maximum values in approximately 3 hours.
9.2 Pharmacodynamics
Effect on thrombosis in animal models
Fondaparinux has dose-dependent antithrombotic activity in a variety of models of experimental thrombosis.
The inhibitory activity varies according to the nature of the thrombotic stimulus and the location of the thrombus i.e. venous (low shear) and arterial (high shear).
Antithrombotic activity is generally achieved at concentrations below those required to saturate plasma ATIII concentrations, with the exception of the inhibition of the thromboplastin-induced thromboembolism which occurs at doses far above antithrombin III-saturating levels. The duration of the antithrombotic activity is correlated with that of anti-factor Xa activity.
Safety Pharmacology
Fondaparinux sodium:
- Showed no relevant effects on the central nervous system
- Did not affect body weight, body temperature and gastro-intestinal motility
- Had no significant effect on electrolyte balance
- Did not induce relevant changes in cardiovascular and respiration parameters
- Did not affect coagulation time, defined as aPTT and PT (see WARNINGS AND PRECAUTIONS, Monitoring, Laboratory and Coagulation Tests), blood cell counts, hemoglobin concentration and hematocrit in animals
- Had little effect on bleeding in the subdermal bleeding model in the rat and in the ear bleeding model in the rabbit at doses that are 25 times higher than the dose resulting in the saturation of antithrombin III (0.8 mg/kg)
- Did not bind to Human Platelet Factor 4 (unlike heparin) and did not cross-react with Heparin Induced Thrombocytopenic (HIT) sera from HIT-patients.
- Did not influence lipid metabolism through the release of triglyceride lipase activity in rats (unlike heparin)
9.3 Pharmacokinetics
Absorption: Following a single 4 mg i.v. bolus administration to normal healthy subjects, mean peak fondaparinux plasma concentration is approximately 0.81 mg/L at the first sampling time point of 5 minutes. After subcutaneous dosing, fondaparinux is completely and rapidly absorbed, with an absolute bioavailability of 100%. Following a single subcutaneous injection of 2.5 mg, peak plasma concentration (Cmax = 0.34 mg/L) is obtained 2 hours post-dosing. Plasma concentrations of half the mean Cmax values are reached 25 minutes post-dosing.
Pharmacokinetics of fondaparinux are linear in the range of 2 to 8 mg by the subcutaneous route. At steady state, mean plasma concentrations 2 hours post dosing ranged between 0.32 and
0.47 mg/L in patients undergoing orthopedic surgeries receiving fondaparinux sodium 2.5 mg.
In patients with symptomatic deep vein thrombosis and pulmonary embolism undergoing treatment with fondaparinux sodium injection 5 mg (body weight < 50 kg), 7.5 mg (body weight 50-100 kg) and 10 mg (body weight > 100 kg) once daily, the body-weight-adjusted doses provide similar exposure across all body weight categories. The peak steady-state plasma concentration is, on average, 1.20-1.26 mg/L. In these patients, the minimum steady-state plasma concentration is 0.46-0.62 mg/L.
Distribution: In healthy adults, intravenously or subcutaneously administered fondaparinux distributes mainly in blood as evidenced by steady state and non-steady state apparent volume of distribution of 7 to 11 L.
In vitro fondaparinux is highly (at least 94% in the concentration range from 0.5 to 2 mg/L) and specifically bound to ATIII and does not bind significantly to other plasma proteins, including Platelet Factor 4 (PF4).
Metabolism: There is no evidence that fondaparinux is metabolized since most of the administered dose is eliminated unchanged in urine.
Elimination: The elimination half life (T1/2) is 17 to 21 hours in healthy subjects.
Up to 77% of a single subcutaneous dose of fondaparinux is excreted in urine as unchanged compound in 72 hours in healthy individuals up to 75 years of age.
Special Populations and Conditions
Pediatrics: The pharmacokinetics of fondaparinux have not been investigated in pediatric patients.
Geriatrics: Fondaparinux elimination is prolonged in patients over 75 years old. In studies evaluating fondaparinux sodium 2.5 mg prophylaxis in hip fracture surgery or elective hip surgery, the total clearance of fondaparinux was approximately 25% lower in patients over 75 years old as compared to patients less than 65 years old. A similar pattern is observed in DVT and PE treatment patients.
Following a single intravenous dose of fondaparinux 4 mg in healthy elderly subjects, a mean Cmax of 0.86 mg/L was observed at the first sampling timepoint of 5 minutes. Other pharmacokinetic parameters following intravenous administration were similar to those observed for subcutaneous administration.
Hepatic Insufficiency: Unbound concentrations of fondaparinux are expected to be unchanged in patients with mild to moderate hepatic insufficiency, and therefore, no dose adjustment is necessary based on pharmacokinetics. Following a single, subcutaneous dose of fondaparinux in subjects with moderate hepatic insufficiency (Child-Pugh Category B), Cmax and AUC were decreased by 22% and 39%, respectively, as compared to subjects with normal liver function. The lower plasma concentrations of fondaparinux were attributed to reduced binding to ATIII secondary to the lower ATIII plasma concentrations in subjects with hepatic insufficiency thereby resulting in increased renal clearance of fondaparinux. There were no clinically relevant differences in the pharmacodynamic measures as assessed by aPTT, PT and ATIII concentrations, indicating that the effect of fondaparinux in subjects with hepatic impairment was similar to that in individuals with normal liver function.
The pharmacokinetics of fondaparinux have not been studied in patients with severe hepatic insufficiency (see DOSAGE AND ADMINISTRATION, Use in Patients with Hepatic Insufficiency and WARNINGS AND PRECAUTIONS).
Renal Insufficiency: Fondaparinux elimination is prolonged in patients with renal insufficiency since the major route of elimination is urinary excretion of unchanged drug. In patients undergoing prophylaxis following elective hip surgery or hip fracture surgery, the total clearance of fondaparinux is approximately 25% lower in patients with mild renal insufficiency (creatinine clearance 50 to 80 mL/min), approximately 40% lower in patients with moderate renal insufficiency (creatinine clearance 30 to 50 mL/min) and approximately 55% lower in patients with severe renal insufficiency (< 30 mL/min) compared to patients with normal renal function. The associated terminal half-life values were 29 hours in moderate and 72 hours in patients with severe renal insufficiency. A similar pattern is observed in DVT and PE treatment patients (see WARNINGS AND PRECAUTIONS, Renal).
Patients Weighing Less Than 50 kg: Total clearance of fondaparinux sodium is decreased by approximately 30% in patients weighing less than 50 kg (see WARNINGS AND PRECAUTIONS, Low Body Weight, and DOSAGE AND ADMINISTRATION, Use in Patients with Low Body Weight).
10 STORAGE, STABILITY AND DISPOSAL
Fondaparinux Sodium Injection should be stored at controlled room temperature 15 °C – 30 °C.
Do not freeze.
If Fondaparinux Sodium Injection is added to a 0.9% saline minibag it should be infused immediately, but can be stored between 15-30 °C for up to 24 hours. Minibags are typically composed of a variety of polymers including PVC, polyethylene, polypropylene, or styrene-ethylene-butadiene, individually or in combination.
11 SPECIAL HANDLING INSTRUCTIONS
Fondaparinux Sodium Injection single dose pre-filled syringes are affixed with an active needle protection system to prevent needle stick injuries following injection. Once the syringe is removed from the injection site, the safety shield is activated manually by firmly pushing the plunger. The protective sleeve will automatically cover the needle.
Keep out of reach and sight of children. Single dose syringes. Discard unused portion.
PART II: SCIENTIFIC INFORMATION
12 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: fondaparinux sodium
Chemical name: methyl O-2-deoxy-6-O-sulfo-2-(sulfoamino)-α-D-glucopyranosyl-(1→ 4)-O-
β-D-glucopyranuronosyl-(1→4)-O-2-deoxy-3,6-di-O-sulfo-2-(sulfoamino) -
α-D-glucopyranosyl-(1 →4)-O-2-O-sulfo-α-L-idopyranuronosyl-(1→4)-2- deoxy-6-O-sulfo-2-(sulfoamino)- α-D-glucopyranoside, decasodium salt
Molecular formula and molecular mass: C31H43N3Na10O49S8
Structural formula:
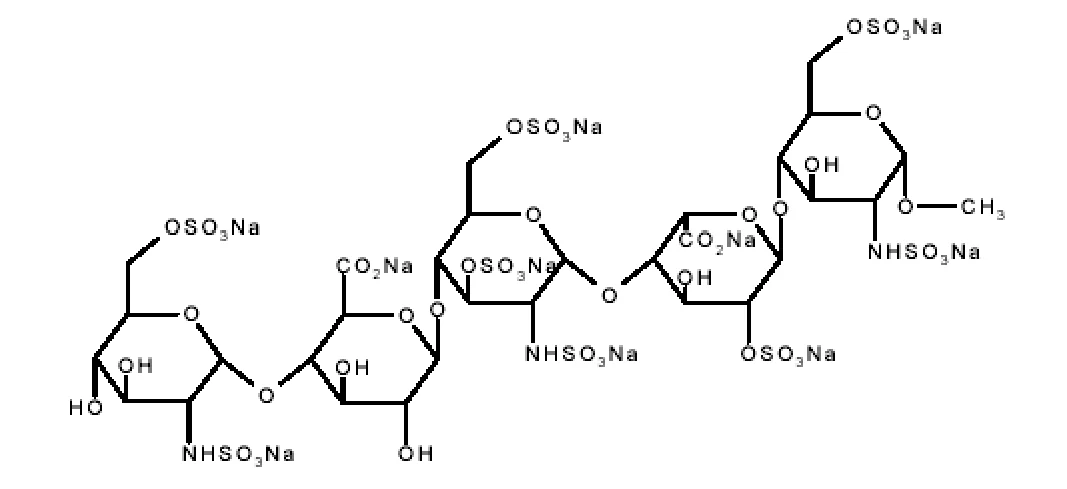
Molecular weight: 1728 g/mol
Physicochemical properties: pH between 5.5 and 7.0 (1.25% w/v in water)
Solubility: Freely soluble in water, 2.0 M Sodium chloride and 0.5 M Sodium hydroxide and insoluble in ethanol
Composition: Each single-dose, prefilled syringe of fondaparinux sodium, affixed with an active needle protection system, contains 2.5 mg of fondaparinux sodium in 0.5 mL, 5 mg of fondaparinux sodium in 0.4 mL, 7.5 mg of fondaparinux sodium in 0.6 mL, or 10 mg of fondaparinux sodium in 0.8 mL of an isotonic solution of sodium chloride, water for injection. Also contains sodium hydroxide or hydrochloric acid for pH adjusters. The final drug product is a clear and colorless to slightly yellow liquid with a pH between 5.5 and 8.0.
13 CLINICAL TRIALS
Prophylaxis of Thromboembolic Events Following Hip Fracture Surgery
Table 15 Summary of Patient Demographics for Clinical Trials in the Prophylaxis of Thromboembolic Events Following Hip Fracture Surgery
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| Randomized, double-blind | 2.5 mg subcutaneous once daily | 1711 | 77 (17-101) | 25% men 75% women |
In a randomized, double-blind, clinical trial in patients undergoing hip fracture surgery, fondaparinux sodium 2.5 mg subcutaneous (SC) once daily was compared to enoxaparin 40 mg SC once daily (the dose of enoxaparin sodium approved for use in prophylaxis in conjunction with orthopedic surgery in Canada is 30 mg SC twice daily).
A total of 1711 patients were randomized and 1673 were treated. Patients ranged in age from 17-101 years (mean age 77 years) with 25% men and 75% women. Patients were 99% Caucasian, 1% other races. Patients with multiple trauma affecting more than one organ system, serum creatinine level more than 180 µmol/L (2 mg/dL), or platelet count less than 100,000/mm3 were excluded from the trial. Fondaparinux sodium was initiated 6 hours after surgery in 88% of patients and the comparator was initiated an average of 18 hours after surgery in 74% of patients. For both drugs, treatment was continued for 7 ± 2 days. Efficacy results are provided in Table 16 below. Major bleeding episodes for both drugs are provided in Table 1 and Table 2 (see ADVERSE REACTIONS).
Table 16 Efficacy Results of Study in the Prophylaxis of Thromboembolic Events Following Hip Fracture Surgery
| Endpoint | Associated value and statistical significance for Fondaparinux sodium 2.5 mg SC once daily1 | Associated value and statistical significance for Enoxaparin 40 mg SC once daily1 | |||||
| All treated Hip Fracture Surgery Patients | N=831 | N=840 | |||||
| All Evaluable2 Hip Fracture Surgery Patients | |||||||
| Venous Thromboembolic Event | 52/626 | 119/624 | |||||
| (VTE3) | 8.3%4 | 19.1% | |||||
| (6.3, 10.8)5 | (16.1, 22.4) | ||||||
| All Deep Vein Thrombosis | 49/624 | 117/623 | |||||
| (DVT) | 7.9%4 | 18.8% | |||||
| (5.9, 10.2) | (15.8, 22.1) | ||||||
| Proximal DVT | 6/650 | 28/646 | |||||
| 0.9%4 | 4.3% | ||||||
| (0.3, 2.0) | (2.9, 6.2) | ||||||
| Symptomatic Pulmonary | 3/831 | 3/840 | |||||
| Embolism (PE) | 0.4%6 | 0.4% | |||||
| (0.1, 1.1) | (0.1, 1.0) | ||||||
- 1 Fondaparinux sodium was initiated 6 hours after surgery in 88% of patients and the enoxaparin was initiated an average of 18 hours after surgery in 74% of patients.
- 2 Evaluable patients were those who were treated and underwent the appropriate surgery (i.e. hip fracture surgery of the upper third of the femur), with an adequate efficacy assessment up to Day 11.
- 3 VTE was a composite of documented DVT and/or documented symptomatic PE reported up to Day 11.
- 4 p-value <0.001
- 5 Number in parentheses indicates 95% confidence interval
- 6 p-value: Not Significant (NS)
Extended Prophylaxis of Thromboembolic Events
Table 17 Summary of Patient Demographics for Clinical Trials in the Extended Prophylaxis of Thromboembolic Events Following Orthopedic Surgery
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| Randomized | 2.5 mg subcutaneous once daily for 7 ± 1 days. At the end of this period, randomized to receive either Fondaparinux Sodium Injection 2.5 mg od or placebo, for 21 ± 2 days. | Fondaparinux sodium: n=737 open period Fondaparinux sodium: n=326 Placebo: n=330 | 75 (23-96) | 29% men 71% women |
In an unblinded manner, 737 patients undergoing hip fracture surgery were initially treated with fondaparinux sodium 2.5 mg once daily for 7 ± 1 days. At the end of this period, 326 patients were randomized to receive fondaparinux sodium 2.5 mg once daily and 330 to placebo in a double-blind trial for 21 ± 2 days; 81 patients were not eligible for randomization. Patients ranged in age from 23 to 96 years (mean age 75 years) and were 29% men and 71% women. Patients were 99% Caucasian and 1% other races. Patients undergoing standard surgery for fracture of the upper third of the femur or the femoral head and neck not more than 48 hours after admission were entered unless they had, mainly, active and significant bleeding, bleeding disorders, creatinine level above 180 mol/L (2.0 mg/dL), received other anticoagulants between admission and surgery and diagnosed deep vein thrombus or pulmonary emboli (PE) during screening or pre- randomization period.
The primary efficacy endpoint was the composite of the following adjudicated VTE outcomes, evaluated during the randomization period up to day 24: symptomatic DVT and/or adjudicated non-fatal PE, and mandatory venogram positive for VTE. The efficacy data are provided in Table 18 below and demonstrate that extended prophylaxis with fondaparinux sodium was associated with a VTE rate of 1.4% compared with a VTE rate of 35.0% for placebo for a relative risk reduction of 95.9% (95% CI=[-99.7; -87.2], p<0.0001). Major bleeding episodes for non-randomized and randomized patients are provided in Table 3 (see ADVERSE REACTIONS, Hemorrhage).
Table 18 Efficacy of Fondaparinux sodium In the Extended Prophylaxis Period (Day 7 ± 1 to Day 28 ± 2) Number and Percentage of Thromboembolic Events in Patients Who had Undergone Hip Fracture Surgery One Week Earlier.1
| Endpoint | Fondaparinux sodium 2.5 mg SC once daily | Placebo SC once daily | |||||
| All Randomized Treated Hip Fracture Surgery Patients | N=326 | N=330 | |||||
| All Randomized Evaluable Hip Fracture Surgery Patients2 | |||||||
| VTE3 | 3/208 | 77/220 | |||||
| 1.4%4 | 35.0% | ||||||
| (0.3, 4.2)5 | (28.7, 41.7) | ||||||
| All DVT | 3/208 | 74/218 | |||||
| 1.4%4 | 33.9% | ||||||
| (0.3, 4.2) | (27.7, 40.6) | ||||||
| Proximal DVT | 2/221 | 35/222 | |||||
| 0.9%4 | 15.8% | ||||||
| (0.1, 3.2) | (11.2, 21.2) | ||||||
| Symptomatic VTE | 1/326 | 9/330 | |||||
| 0.3%6 | 2.7% | ||||||
| (0.1, 1.7) | (1.3, 5.1) | ||||||
- 1 During the one week pre-randomization period preceding the Extended Prophylaxis Period all patients had been treated with open-label fondaparinux sodium 2.5 mg SC once daily.
- 2 Evaluable patients were those who were treated in the post-randomization period, with an adequate efficacy assessment up to Day 24 following randomization.
- 3 VTE was a composite of documented DVT and/or documented symptomatic PE reported up to Day 24 following randomization.
- 4 p-value <0.001
- 5 Number in parentheses indicates 95% confidence interval
- 6 p-value = 0.021
Prophylaxis of Thromboembolic Events following Hip Replacement Surgery
Table 19 Summary of Patient Demographics for Clinical Trials in the Prophylaxis of Thromboembolic Events Following Hip Replacement Surgery
| Study # | Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| 1 | Randomized, double-blind | 2.5 mg fondaparinux subcutaneous once daily vs. 30 mg enoxaparin bid. | 2275 | 65 (18-92) | 48% men 52% women |
| 2 | Randomized, double-blind | 2.5 mg fondaparinux subcutaneous once daily vs. 40 mg enoxaparin once daily | 2309 | 65 (24-97) | 42% men 58% women |
In two randomized, double-blind, clinical trials in patients undergoing hip replacement surgery, fondaparinux sodium 2.5 mg SC once daily was compared to either enoxaparin sodium 30 mg SC every 12 hours (Study 1) or to enoxaparin sodium 40 mg SC once a day (Study 2). The dose of enoxaparin sodium approved for prophylaxis in conjunction with orthopedic surgery in Canada is 30 mg SC twice daily. In Study 1, a total of 2,275 patients were randomized and 2,257 were treated. Patients ranged in age from 18 to 92 years (mean age 65 years) with 48% men and 52% women. Patients were 94% Caucasian, 4% Black, <1% Asian, and 2% others. In Study 2, a total of 2,309 patients were randomized and 2,273 were treated. Patients ranged in age from 24 to 97 years (mean age 65 years) with 42% men and 58% women. Patients were 99% Caucasian, and 1% other races. Patients with serum creatinine level more than 180 µmol/L (2 mg/dL), or platelet count less than 100,000/mm3 were excluded from both trials.
In Study 1, fondaparinux sodium was initiated 6 ± 2 hours (mean 6.5 hrs) after surgery in 92% of patients and enoxaparin sodium was initiated 12 to 24 hours (mean 20.25 hrs) after surgery in 97% of patients. In Study 2, fondaparinux sodium was initiated 6 ± 2 hours (mean 6.25 hrs) after surgery in 86% of patients and enoxaparin sodium was initiated 12 hours before surgery in 78% of patients. The first post-operative enoxaparin sodium dose was given before 12 hours after surgery in 60% of patients and 12 to 24 hours after surgery in 35% of patients with a mean of 13 hrs. For both studies, both study treatments were continued for 7 ± 2 days. Efficacy results are provided in Table 20 below. Major bleeding episodes for both drugs are provided in Table 1 and Table 2 (see ADVERSE REACTIONS).
Table 20 Efficacy Results of Study in the Prophylaxis of Thromboembolic Events Following Hip Replacement Surgery
| Endpoint | Study 1 | Study 2 | ||||||||||||||||
Fondaparinux sodium 2.5 mg SC once daily1 | Enoxaparin 30 mg SC every 12 hr2 | Fondaparinux sodium 2.5 mg SC once daily1 | Enoxaparin 40 mg SC once daily3 | |||||||||||||||
| All Treated Hip Replacement Surgery Patients | ||||||||||||||||||
| N=1126 | N=1128 | N=1129 | N=1123 | |||||||||||||||
| All Evaluable4 Hip Replacement Surgery Patients | ||||||||||||||||||
| VTE5 | 48/787 | 66/797 | 37/908 | 85/919 | ||||||||||||||
| 6.1%6 | 8.3% | 4.1%9 | 9.2% | |||||||||||||||
| (4.5, 8.0)7 | (6.5, 10.4) | (2.9, 5.6) | (7.5, 11.3) | |||||||||||||||
| All DVT | 44/784 | 65/796 | 36/908 | 83/918 | ||||||||||||||
| 5.6%8 | 8.2% | 4.0%9 | 9.0% | |||||||||||||||
| (4.1, 7.5) | (6.4, 10.3) | (2.8, 5.4) | (7.3, 11.1) | |||||||||||||||
| Proximal DVT | 14/816 | 10/830 | 6/922 | 23/927 | ||||||||||||||
| 1.7%6 | 1.2% | 0.7%9 | 2.5% | |||||||||||||||
| (0.9, 2.9) | (0.6, 2.2) | (0.2, 1.4) | (1.6, 3.7) | |||||||||||||||
| Symptomatic PE | 5/1126 | 1/1128 | 2/1129 | 2/1123 | ||||||||||||||
| 0.4%6 | 0.1% | 0.2%6 | 0.2% | |||||||||||||||
| (0.1, 1.0) | (0.0, 0.5) | (0.0, 0.6) | (0.0, 0.6) | |||||||||||||||
- 1 Patients randomized to fondaparinux sodium 2.5 mg were to receive the first injection 6 ± 2 hours after surgery providing that hemostasis had been achieved.
- 2 Patients randomized to enoxaparin sodium were to receive the first injection between 12 and 24 hours after surgery.
- 3 Patients randomized to enoxaparin sodium were to receive the first injection 12 hours prior to surgery except in the case of spinal anesthesia. The first post-operative enoxaparin sodium dose was to be given between 12 to 24 hours after surgery.
- 4 Evaluable patients were those who were treated and underwent the appropriate surgery (i.e. elective hip replacement surgery), with an adequate efficacy assessment up to Day 11.
- 5 VTE was a composite of documented DVT and/or documented symptomatic PE reported up to Day 11.
- 6 p-value versus enoxaparin sodium: NS
- 7 Number in parentheses indicates 95% confidence interval
- 8 p-value versus enoxaparin sodium in study 1: <0.05
- 9 p-value versus enoxaparin sodium in study 2: <0.01
Prophylaxis of Thromboembolic Events following Knee Replacement Surgery
Table 21 Summary of Patient Demographics for Clinical Trials in the Prophylaxis of Thromboembolic Events Following Knee Replacement Surgery
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
Randomized, double-blind | 2.5 mg fondaparinux subcutaneous once daily vs. 30 mg enoxaparin SC bid. | 1049 | 68 (19-94) | 41% men 59% women |
In a randomized, double-blind, clinical trial in patients undergoing knee replacement surgery (i.e., surgery requiring resection of the distal end of the femur or proximal end of the tibia), fondaparinux sodium 2.5 mg SC once daily was compared to enoxaparin sodium 30 mg SC every
12 hours. A total of 1,049 patients were randomized and 1,034 were treated. Patients ranged in age from 19 to 94 years (mean age 68 years) with 41% men and 59% women. Patients were 88% Caucasian, 8% Black, <1% Asian, and 3% others. Patients with serum creatinine level more than 180 µmol/L (2 mg/dL), or platelet count less than 100,000/mm3 were excluded from the trial. Fondaparinux sodium was initiated 6 ± 2 hours (mean 6.25 hrs) after surgery in 94% of patients and enoxaparin sodium was initiated 12 to 24 hours (mean 21 hrs) after surgery in 96% of patients. For both drugs, treatment was continued to 7 ± 2 days. Efficacy results are provided in Table 22 below. Major bleeding episodes for both drugs are provided in Table 1 and Table 2
(see ADVERSE REACTIONS).
Table 22 Efficacy Results of Study in the Prophylaxis of Thromboembolic Events Following Knee Replacement Surgery
| Endpoint | Fondaparinux sodium1 | Enoxaparin2 | ||||
| All treated Knee Replacement Surgery Patients | N=517 | N=517 | ||||
| All Evaluable3 Knee Replacement Surgery Patients | ||||||
| VTE4 | 45/361 | 101/363 | ||||
| 12.5%5 | 27.8% | |||||
| (9.2, 16.3)6 | (23.3, 32.7) | |||||
| All DVT | 45/361 | 98/361 | ||||
| 12.5%5 | 27.1% | |||||
| (9.2, 16.3) | (22.6, 32.0) | |||||
| Proximal DVT | 9/368 | 20/372 | ||||
| 2.4%7 | 5.4% | |||||
| (1.1, 4.6) | (3.3, 8.2) | |||||
| Symptomatic PE | 1/517 | 4/517 | ||||
| 0.2%7 | 0.8% | |||||
| (0.0, 1.1) | (0.2, 2.0) | |||||
- 1 Patients randomized to fondaparinux sodium 2.5 mg received the first injection 6 ± 2 hours after surgery providing that hemostasis had been achieved.
- 2 Patients randomized to enoxaparin sodium received the first injection at 21 ± 2 hours after surgery closure providing that hemostasis had been achieved.
- 3 Evaluable patients were those who were treated and underwent the appropriate surgery (i.e. knee replacement surgery), with an adequate efficacy assessment up to Day 11.
- 4 VTE was a composite of documented DVT and/or documented symptomatic PE reported up to Day 11.
- 5 p-value <0.001
- 6 Number in parentheses indicates 95% confidence interval
- 7 p-value: NS
Prophylaxis of Thromboembolic Events following Abdominal Surgery
In a double-blind, double-dummy clinical trial, 2,927 patients at high risk of thromboembolic complication while undergoing abdominal surgery were randomized to fondaparinux sodium 2.5 mg SC once daily started 6 hours postoperatively or dalteparin sodium 5,000 IU SC once daily (2,500 IU SC 2 hours before and a 2,500 IU SC 12 hours after operation on the first day). Both treatments were given for 5 to 9 days to 2,858 patients who were then followed-up for one month. Patients were 17 to 93 years (mean age 65 years), 55% were men and 97% were Caucasian. Patients undergoing urological (other than kidney), gynaecological, vascular, or laparoscopic surgery were excluded.
While it had been originally planned to include any patients at high risk of venous thomboembolic events (VTE) when undergoing abdominal surgery, it was noted during a blinded review of the data that VTE rate was lower than expected. It was then decided to recruit mainly cancer patients as these patients have a higher risk of VTE. Sixty-nine percent (69%) of study patients underwent cancer-related abdominal surgery.
The study was initially designed to show superiority of fondaparinux sodium over dalteparin. Assuming a frequency of VTE of 7% with dalteparin, 1,000 evaluable patients per treatment group would give a power greater than 75% to detect a targeted relative risk reduction of 40%. However, it was observed early after the start of the study that the VTE rate was much lower than anticipated and that since this trend continued until the end, it became evident that superiority could not be demonstrated. The Steering Committee decided at the very end, but before database lock-up and un-blinding, to also perform a non-inferiority analysis. The results of two meta-analyses were used to determine the non-inferiority margin. One meta-analysis evaluated the effects of perioperative administration of subcutaneous heparin compared to placebo on VTE and pulmonary embolism. The other and more pertinent meta-analysis used the results of studies comparing the effects of low molecular weight heparins and heparin on VTE in patients undergoing general and cancer surgery. An indirect confidence interval method was used to select a non-inferiority margin of 1.7 (odds ratio) which corresponds to preserving 63% of the minimal effect expected with low molecular weight heparins.
In all evaluable patients (N=2,058), the incidence of total venous thromboembolic events with fondaparinux sodium was 4.6% (47/1,027) and with dalteparin was 6.1% (62/1,021) for an absolute risk reduction of 1.5% and odds ratio reduction of 25.8% (95% CI: -9.5%, +49.7%). The difference in total VTE between the two groups was not statistically significant and was mainly due to a reduction in asymptomatic distal deep vein thrombosis (DVT). The incidence of symptomatic DVT was similar between the groups: 6/1,027 (0.4%) in the fondaparinux sodium group and 5/1,021 (0.3%) in the dalteparin group. In patients undergoing cancer surgery, 69% of the 2058 evaluable patients, the VTE rate was 4.7% in the fondaparinux sodium group and 7.7% in the dalteparin group.
Major bleeding was observed in 3.4% (49/1,433) of the fondaparinux sodium treated patients and 2.4% (34/1,425) of the dalteparin-treated patients. For other bleeding events see Table 4 under ADVERSE REACTIONS - Prophylaxis of VTE following abdominal surgery. See also WARNINGS AND PRECAUTIONS - Renal - Prophylaxis of VTE following orthopedic or abdominal surgery.
Treatment of Deep Vein Thrombosis and Pulmonary Embolism
The fondaparinux sodium clinical program in treatment of venous thromboembolism was designed to demonstrate the efficacy of fondaparinux sodium for the treatment of deep vein thrombosis (DVT) and pulmonary embolism (PE). Over 4,874 patients were studied in controlled Phase II and III clinical studies.
Treatment of Deep Vein Thrombosis
Table 23 Summary of Patient Demographics for Clinical Trial in the Treatment of Deep Vein Thrombosis
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| Randomized, double-blind | 5 mg (body wt < 50 kg) 7.5 mg (body wt 50 - 100 kg) 10 mg (body wt > 100 kg) fondaparinux subcutaneous once daily vs. 1 mg/kg enoxaparin SC every 12 hours | 2205 | 61 (18-95) | 53% men 47% women |
In a randomized, double-blind, clinical trial in patients with a confirmed diagnosis of acute symptomatic DVT, fondaparinux sodium 5 mg (body weight < 50 kg), 7.5 mg (body weight 50-100 kg) or 10 mg (body weight > 100 kg) SC once daily (fondaparinux sodium treatment regimen) was compared to enoxaparin sodium 1 mg/kg SC every 12 hours in both hospitalized and non-hospitalized patients. Outpatient and home treatment of fondaparinux sodium was permitted, and approximately 32% of patients were discharged home from the hospital while receiving fondaparinux therapy.
A total of 2,205 patients were randomized and 2,192 were treated. Patients ranged in age from 18-95 years (mean age 61 years) with 53% men and 47% women. Patients were 97% Caucasian, 2% Black and 1% other races. For both groups, treatment continued for at least 5 days, and both treatment groups received Vitamin K antagonist therapy initiated within 72 hours after the first study drug administration and continued for 90 ± 7 days, with regular dose adjustments to achieve an INR of 2-3. The primary efficacy endpoint was confirmed, symptomatic, recurrent VTE reported up to Day 97. Treatment with fondaparinux sodium was associated with a VTE rate of 3.9% compared with a VTE rate of 4.1% for enoxaparin sodium. The efficacy data are provided in Table 24 below.
Table 24 Efficacy of Fondaparinux Sodium Injection In the Treatment of Deep Vein Thrombosis
| Endpoint | Fondaparinx sodium1 5, 7.5 or 10 mg SC once daily (Treatment Regimen) | Enoxaparin Sodium1 1 mg/kg SC q 12h |
| All Randomized DVT Patients | N=1098 | N=1107 |
| Total VTE2 | 433 (3.9%) | 45 (4.1%) |
| DVT only | 18 (1.6%) | 28 (2.5%) |
| Non-fatal PE | 20 (1.8%) | 12 (1.1%) |
| Fatal VTE | 5 (0.5%) | 5 (0.5%) |
- 1 Patients were also treated with vitamin K antagonists initiated within 72 hours after the first study drug administration.
- 2 VTE was a composite of symptomatic recurrent VTE or fatal VTE reported up to Day 97.
- 3 The 95% confidence interval for the treatment difference for total VTE was: -1.8% to 1.5%.
Treatment of Pulmonary Embolism
Table 25 Summary of Patient Demographics for Clinical Trial in the Treatment of Pulmonary Embolism
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender |
| Randomized, open label | 5 mg (body wt < 50 kg) 7.5 mg (body wt 50 - 100 kg) 10 mg (body wt > 100 kg) fondaparinux subcutaneous once daily vs. heparin IV bolus (5000 units) followed by aPPT adjusted continuous IV infusion | 2213 | 62 (18-97) | 44% men 56% women |
In a randomized, open-label, clinical trial in patients with a confirmed diagnosis of acute symptomatic PE, with or without DVT, fondaparinux sodium 5 mg (body weight < 50 kg), 7.5 mg (body weight 50-100 kg) or 10 mg (body weight > 100 kg) SC once daily (fondaparinux sodium treatment regimen) was compared to heparin IV bolus (5,000 units) followed by a continuous IV infusion adjusted to maintain 1.5-2.5 times aPTT control value. Outpatient and home treatment of fondaparinux sodium was permitted, and approximately 15% of patients were discharged home from the hospital while receiving fondaparinux therapy.
A total of 2,213 patients were randomized and 2,184 were treated. Patients ranged in age from 18-97 years (mean age 62 years) with 44% men and 56% women. Patients were 94% Caucasian, 5% Black and 1% other races. For both groups, treatment continued for at least 5 days, and both treatment groups received Vitamin K antagonist therapy initiated within 72 hours after the first study drug administration and continued for 90 ± 7 days, with regular dose adjustments to achieve an INR of 2-3. The primary efficacy endpoint was confirmed, symptomatic, recurrent VTE reported up to Day 97. Treatment with fondaparinux sodium was associated with a VTE rate of 3.8% compared with a VTE rate of 5.0% for unfractionated heparin. The efficacy data are provided in Table 26 below.
Table 26 Efficacy of Fondaparinux Sodium Injection in the Treatment of Pulmonary Embolism
| Endpoint | Fondaparinx sodium1 5, 7.5 or 10 mg SC once daily (Treatment Regimen) | Heparin1 aPTT adjusted IV |
| All Randomized PE Patients | N=1103 | N=1110 |
| Total VTE2 | 423 (3.8%) | 56 (5.0%) |
| DVT only | 12 (1.1%) | 17 (1.5%) |
| Non-fatal PE | 14 (1.3%) | 24 (2.2%) |
| Fatal VTE | 16 (1.5%) | 15 (1.4%) |
- 1 Patients were also treated with vitamin K antagonists initiated within 72 hours after the first study drug administration.
- 2 VTE was a composite of symptomatic recurrent VTE or fatal VTE reported up to Day 97.
- 3 The 95% confidence interval for the treatment difference for total VTE was: -3.0% to 0.5%.
Management of Unstable Angina or Non-ST Segment Elevation Myocardial Infarction (UA/NSTEMI)
In a randomized, double-blind, outcome trial, OASIS 5, 20,078 subjects presenting to hospital with suspected UA/NSTEMI acute coronary syndrome and at least 2 of 3 risk criteria (aged ≥60 years, troponin T or I or CK-MB above the upper limit of normal, or ECG changes compatible with ischemia) were randomized to fondaparinux sodium (n=10,057) or enoxaparin (n=10,021) within 24 hours of the most recent episode of symptoms. Patients were to be eligible for anticoagulation treatment.
Table 27 Summary of Patient Demographics in OASIS 5 1,2
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | |||||
| Randomized, | 2.5 mg fondaparinux | 20078 | 67 | 62% men | |||||
| double-blind, non- | SC once daily for up | (21-98) | 38% | ||||||
| inferiority outcome | to 8 days or discharge | women | |||||||
| trial | |||||||||
| 1 mg/kg enoxaparin | |||||||||
| SC twice daily (once | |||||||||
| daily if creatinine | |||||||||
| clearance was | |||||||||
| between 20 mL/min | |||||||||
| and 30 mL/min) for | |||||||||
| 2-8 days or until | |||||||||
| clinically stable | |||||||||
- 1 45% of subjects had UA, and 55% had NSTEMI.
- 2 Approximately 40% and 17% of patients had mild (creatinine clearance 50 to <80 mL/min) or moderate (creatinine clearance 30 to <50 mL/min) renal insufficiency, respectively, at randomization.
Patients received standard medical care for UA/NSTEMI including acetylsalicylic acid, clopidogrel/ ticlopidine, GPIIb/IIIa inhibitors, as well as percutaneous coronary intervention (PCI) or coronary artery bypass graft (CABG) surgery, where appropriate. Patients undergoing PCI received either a single pre-procedural dose of fondaparinux sodium intravenously (fondaparinux sodium treatment arm) or unfractionated heparin intravenously (enoxaparin treatment arm) using an algorithm based on the time of the previous subcutaneous dose and whether GPIIb/IIIa inhibitors were planned. Subcutaneous study drug was resumed after PCI if possible. Patients undergoing CABG surgery had study drug temporarily stopped 24 hours prior to surgery and restarted 48 hours post surgery, if possible.
The objective of the study was to determine whether fondaparinux sodium was non-inferior to enoxaparin within 9 days of randomization based on the primary composite endpoint of death, myocardial infarction (MI) and refractory ischemia (RI) (see Table 28).
Table 28 Efficacy of Fondaparinux sodium in the Treatment of UA/NSTEMI up to Day 9 in OASIS 5 (All Randomized Patients)
| Endpoint | Fondapariux sodium1 N=10 057 | Enoxaparin2 N=10 021 | Hazard Ratio (95% CI) |
| Death or MI or RI3 | 579 (5.8%) | 574 (5.7%) | 1.01 (0.90, 1.13)4 |
| Death | 177 (1.8%) | 186 (1.9%) | 0.95 (0.77, 1.17) |
| MI | 263 (2.6%) | 264 (2.6%) | 0.99 (0.84, 1.18) |
| RI | 194 (1.9%) | 189 (1.7%) | 1.02 (0.84, 1.25) |
- 1 Patients randomized to fondaparinux sodium received 2.5 mg fondaparinux SC once daily for up to 8 days or discharge.
- 2 Patients randomized to enoxaparin sodium received 1 mg/kg enoxaparin SC twice daily (once daily if creatinine clearance was between 20 mL/min and 30 mL/min) for 2-8 days or until clinically stable.
- 3 The primary endpoint was a composite of death, myocardial infarction (MI) and refractory ischemia (RI) within 9 days of randomization.
- 4 p=0.003, one-sided non-inferiority.
Fondaparinux sodium was as effective as enoxaparin in reducing the risk of death, MI or refractory ischemia at Day 9 (see Table 28 and Table 29). The treatment effect observed for the components was consistent with that for the overall composite endpoint (see Table 28). At 6 month follow-up, the benefit of fondaparinux sodium was maintained (Table 29).
Table 29 Efficacy of Fondaparinux sodium for the Prevention of Death, MI or RI in UA/NSTEMI up to Day 180 in OASIS 5 (All Randomized Patients)
| Endpoint | Fondaparinux sodium 1 N=10 057 | Enoxaparin2 N=10 021 | Hazard Ratio (95% CI) | P-value |
| Day 93 | 579 (5.8%) | 574 (5.7%) | 1.019 (0.90, 1.13) | p=0.9234 |
| Day 14 | 658 (6.5%) | 701 (7.0%) | 0.94 (0.84, 1.04) | p=0.222 |
| Day 30 | 806 (8.0%) | 865 (8.6%) | 0.93 (0.84, 1.02) | p=0.127 |
| Day 90 | 1044 (10.4%) | 1112 (11.1%) | 0.93 (0.86, 1.02) | p=0.110 |
| Day 180 | 1223 (12.2%) | 1309 (13.1%) | 0.93 (0.86, 1.00) | p=0.063 |
- 1 Patients randomized to fondaparinux sodium received 2.5 mg fondaparinux SC once daily for up to 8 days or discharge.
- 2 Patients randomized to enoxaparin sodium received 1 mg/kg enoxaparin SC twice daily (once daily if creatinine clearance was between 20 mL/min and 30 mL/min) for 2-8 days or until clinically stable.
- 3 The primary endpoint was a composite of death, myocardial infarction (MI) and refractory ischemia (RI) within 9 days of randomization.
- 4 p=0.003, one-sided non-inferiority.
In the management of UA/NSTEMI with fondaparinux sodium, the risk of all cause mortality up to Day 180 is reported in Table 30.
Table 30 Efficacy of Fondaparinux sodium for the Prevention of All Cause Mortality in UA/NSTEMI up to Day 180 in OASIS 5 (All Randomized Patients)
| Endpoint | Fondaparinux sodium1 N=10 057 | Enoxaparin2 N=10 021 | Hazard Ratio (95% CI) | P-value |
| Day 9 | 177 (1.8%) | 186 (1.9%) | 0.95 (0.77, 1.17) | 0.614 |
| Day 14 | 211 (2.1%) | 242 (2.4%) | 0.87 (0.72, 1.04) | 0.135 |
| Day 30 | 295 (2.9%) | 352 (3.5%) | 0.83 (0.71, 0.97) | 0.022 |
| Day 90 | 460 (4.6%) | 510 (5.1%) | 0.90 (0.79, 1.02) | 0.089 |
| Day 180 | 574 (5.7%) | 638 (6.4%) | 0.89 (0.80, 1.00) | 0.052 |
- 1 Patients randomized to fondaparinux sodium received 2.5 mg fondaparinux SC once daily for up to 8 days or discharge.
- 2 Patients randomized to enoxaparin sodium received 1 mg/kg enoxaparin SC twice daily (once daily if creatinine clearance was between 20 mL/min and 30 mL/min) for 2-8 days or until clinically stable.
The rates of major bleeding episodes for UA/NSTEMI patients treated with fondaparinux sodium vs. enoxaparin are provided in Table 6 and Table 7 (see ADVERSE REACTIONS).
In patients undergoing PCI during the initial hospitalization, the relative effects of fondaparinux sodium and enoxaparin on death, MI or refractory ischemia and on major bleeding at Day 9 were consistent with that observed for the overall population (see Table 31 and Table 32). However, in patients undergoing PCI, the incidence of guiding catheter thrombosis, although rare, was higher in patients treated with fondaparinux sodium compared to enoxaparin (see WARNINGS AND PRECAUTIONS, Cardiovascular, and ADVERSE REACTIONS, Management of UA/NSTEMI, Risk of catheter thrombosis during PCI).
Table 31 Efficacy of Fondaparinux sodium by PCI Usage During Initial Hospitalisation up to Day 9 and Day 180 in OASIS 5 (All Randomized Patients)
| Fondaparinux Sodium | Enoxaparin | HR (95% CI) | |||||||||||||||
| Death/MI/RI* | n | N | % | n | N | % | |||||||||||
| Day 9 | Overall | 579 | 10057 | 5.8 | 574 | 10021 | 5.7 | 1.01 (0.90, 1.13) | |||||||||
| PCI use: | Yes | 305 | 3454 | 8.8 | 282 | 3435 | 8.2 | 1.08 (0.92, 1.27) | |||||||||
| No | 274 | 6597 | 4.2 | 292 | 6585 | 4.4 | 0.94 (0.79, 1.10) | ||||||||||
| Day 180 | Overall | 1223 | 10057 | 12.2 | 1309 | 10021 | 13.1 | 0.93 (0.86, 1.00) | |||||||||
| PCI use: | Yes | 448 | 3454 | 13.0 | 438 | 3435 | 12.8 | 1.02 (0.89, 1.16) | |||||||||
| No | 775 | 6597 | 11.7 | 871 | 6585 | 13.2 | 0.88 (0.80, 0.97) | ||||||||||
| Death/MI | |||||||||||||||||
| Day 9 | Overall | 409 | 10057 | 4.1 | 412 | 10021 | 4.1 | 0.99 (0.86, 1.13) | |||||||||
| PCI use: | Yes | 196 | 3454 | 5.7 | 185 | 3435 | 5.4 | 1.05 (0.86, 1.29) | |||||||||
| No | 213 | 6597 | 3.2 | 227 | 6585 | 3.4 | 0.94 (0.78, 1.13) | ||||||||||
| Day 180 | Overall | 1042 | 10057 | 10.4 | 1127 | 10021 | 11.2 | 0.92 (0.84, 1.00) | |||||||||
| PCI use: | Yes | 332 | 3454 | 9.6 | 333 | 3435 | 9.7 | 0.99 (0.85, 1.16) | |||||||||
| No | 710 | 6597 | 10.8 | 794 | 6585 | 12.1 | 0.89 (0.80, 0.98) | ||||||||||
| Death alone | |||||||||||||||||
| Day 9 | Overall | 177 | 10057 | 1.8 | 186 | 10021 | 1.9 | 0.95 (0.77, 1.17) | |||||||||
| PCI use: | Yes | 37 | 3454 | 1.1 | 38 | 3435 | 1.1 | 0.97 (0.62, 1.52) | |||||||||
| No | 140 | 6597 | 2.1 | 148 | 6585 | 2.2 | 0.94 (0.75, 1.19) | ||||||||||
| Day 180 | Overall | 574 | 10057 | 5.7 | 638 | 10021 | 6.4 | 0.89 (0.80, 1.00) | |||||||||
| PCI use: | Yes | 113 | 3454 | 3.3 | 121 | 3435 | 3.5 | 0.93 (0.72, 1.20) | |||||||||
| No | 461 | 6597 | 7.0 | 517 | 6585 | 7.9 | 0.89 (0.78, 1.01) | ||||||||||
* The primary endpoint was a composite of death, myocardial infarction (MI) and refractory ischemia (RI) up to and including Day 9
Table 32 Adjudicated Major Bleeding by PCI Usage During Initial Hospitalisation (As Treated Patients) in OASIS 5
| Fondaparinux sodium | Enoxaparin | HR (95% CI) | P-value | ||||||||||||||
| n | N | % | n | N | % | ||||||||||||
| On Therapy1 | Overall | 183 | 9979 | 1.8 | 389 | 9969 | 3.9 | 0.38 (0.29, 0.49) | <0.001 | ||||||||
| PCI use: | Yes | 66 | 3422 | 1.9 | 165 | 3410 | 4.8 | 0.39 (0.29, 0.52) | |||||||||
| No | 117 | 6555 | 1.8 | 224 | 6559 | 3.4 | 0.51 (0.41, 0.64) | ||||||||||
| Day 9 | Overall | 209 | 9979 | 2.1 | 406 | 9969 | 4.1 | 0.51 (0.43, 0.60) | <0.001 | ||||||||
| PCI use: | Yes | 74 | 3422 | 2.2 | 169 | 3410 | 5.0 | 0.43 (0.33, 0.57) | |||||||||
| No | 135 | 6555 | 2.1 | 237 | 6559 | 3.6 | 0.57 (0.46, 0.70) | ||||||||||
1 The on therapy period was from the start of dosing at randomization until 2 days post the last injection.
Management of ST segment Elevation Myocardial Infarction (STEMI)
In OASIS 6 a randomized, double-blind, outcome trial, , fondaparinux sodium was compared to usual care (placebo or UFH) in 12,092 subjects presenting to hospital with STEMI acute coronary syndrome within 12 hours of symptom onset. Randomization was stratified according to whether UFH was indicated based on the judgement of the investigator. A total of 5,658 patients were enrolled in Stratum 1 who received fondaparinux sodium (n=2,823) or placebo (n=2,835) and 6,434 patients were enrolled in Stratum 2 who received fondaparinux sodium (n=3,213) or UFH (n=3,221).
Table 33 Summary of Patient Demographics in OASIS 61
| Trial design | Dosage, route of administration and duration | Study subjects (n=number) | Mean age (Range) | Gender | |||||
| Randomized, | 2.5 mg fondaparinux | 12 092 | 61 | 72% men | |||||
| double-blind, | SC once daily for up | (22-96) | 28% | ||||||
| superiority outcome | to 8 days or | women | |||||||
| trial | discharge, initial dose | ||||||||
| 2.5 mg IV bolus | |||||||||
| Usual care | |||||||||
| Stratum 1: placebo | |||||||||
| Stratum 2: UFH 60 | |||||||||
| IU/kg IV bolus | |||||||||
| followed by 12 | |||||||||
| IU/kg/hr infusion for | |||||||||
| 24-48 hours (IV bolus | |||||||||
| only in primary PCI | |||||||||
| patients) | |||||||||
1 Approximately 40% and 14% of patients had mild (creatinine clearance 50 to <80 mL/min) or moderate (creatinine clearance 30 to <50 mL/min) renal insufficiency, respectively, at randomization.
The primary adjudicated endpoint was a composite of death and reinfarction (recurrent myocardial infarction) within 30 days of randomization. The results for fondaparinux sodium compared to control (UFH or placebo combined) at Day 30 were 9.7% vs. 11.1% for death or myocardial reinfarction (p=0.008), 7.8% vs. 8.9% for death (all cause mortality) (p=0.023), and 2.3% vs. 2.8% for myocardial reinfarction (p=0.069) (see Table 34).
Table 34 Efficacy of Fondaparinux sodium in the Treatment of STEMI up to Day 30 in OASIS 6 (All Randomized Patients)
| Overall | Stratum 1 | Stratum 2 | ||||||||||||||||||||||
| Endpoint | Fondapariu x sodium1 N=6036 | Control2 N=6056 | Hazard Ratio3 (95% CI) | Fondaparinux sodium N=2823 | Placebo5 N=2835 | Hazard Ratio3 (95% CI) | Fondaparinx sodium N=3213 | UFH N=3221 | Hazard Ratio3 (95% CI) | |||||||||||||||
| Death/ | 584 | 675 | 0.86 | 318 | 396 | 0.80 | 266 | 279 | 0.94 | |||||||||||||||
| Reinfarction4 | (9.7%) | (11.1%) | (0.77, 0.96) | (11.3%) | (14.0%) | (0.60, 0.93) | (8.3%) | (8.7%) | (0.79, 1.11) | |||||||||||||||
| Death | 470 (7.8%) | 541 (8.9%) | 0.87 (0.77, 0.98) | 257 (9.1%) | 321 (11.3%) | 0.80 (0.68, 0.94) | 213 (6.6%) | 220 (6.8%) | 0.95 (0.79, 1.15) | |||||||||||||||
| Reinfarcton | 141 (2.3%) | 172 (2.8%) | 0.81 (0.65, 1.02) | 74 (2.6%) | 92 (3.2%) | 0.79 (0.58, 1.07) | 67 (2.1%) | 80 (2.5%) | 0.83 (0.60, 1.15) | |||||||||||||||
- 1 Patients randomized to fondaparinux sodium received an IV bolus injection of 2.5 mg followed by 2.5 mg by SC injection daily for up to 8 days or discharge.
- 2 Patients randomized to UFH received an IV bolus injection 60 IU/kg followed by an infusion of 12 IU/kg/hr for 24 to 48 hours.
- 3 The hazard ratio, fondaparinux sodium versus control, was adjusted for treatment group and strata.
- 4 The primary endpoint was a composite of death and reinfarction within 30 days of randomization.
5 Placebo patients did not receive unfractionated heparin as an anticoagulant.
The treatment effect was greater with fondaparinux sodium than with control (UFH or placebo combined) in reducing the risk of death or reinfarction at Day 30 (see Table 34). The treatment effect observed for the components was consistent with that for the overall composite endpoint (see Table 34). At 6 month follow-up, the benefit of fondaparinux sodium was maintained (see Table 35).
Table 35 Efficacy of Fondaparinux sodium for the Prevention of Death or Reinfarction in STEMI up to 6 Months in OASIS 6 (All Randomized Patients)
| Overall | Stratum 1 | Stratum 2 | |||||||||||||
| Endpoint | Fondaparinux sodium1 N=6036 | Control2 N=6056 | Hazard Ratio3 (95% CI) | Fondaparinux sodium N=2823 | Placebo4 N=2835 | Hazard Ratio3 (95% CI) | Fondaparinx sodium N=3213 | UFH2 N=3221 | Hazard Ratio3 (95% CI) | ||||||
| Day 9 | 443 (7.3%) | 536 (8.9%) | 0.82 (0.73, 0.93) | 240 (8.5%) | 314 (11.1%) | 0.76 (0.64, 0.90) | 203 (6.3%) | 222 (6.9%) | 0.91 (0.75, 1.10) | ||||||
| Day 30 | 584 (9.7%) | 675 (11.1%) | 0.86 (0.77, 0.96) | 318 (11.3%) | 396 (14.0%) | 0.80 (0.69, 0.93) | 266 (8.3%) | 279 (8.7%) | 0.94 (0.79, 1.11) | ||||||
| Day 90 | 683 (11.3%) | 796 (13.1%) | 0.85 (0.77, 0.94) | 369 (13.1%) | 441 (15.6%) | 0.83 (0.72, 0.95) | 314 (9.8%) | 355 (11.0%) | 0.87 (0.75, 1.02) | ||||||
| Day 180 | 756 (12.5%) | 855 (14.1%) | 0.88 (0.79, 0.97) | 414 (14.7%) | 469 (16.5%) | 0.87 (0.77, 1.00) | 342 (10.6%) | 386 (12.0%) | 0.87 (0.75, 1.01) | ||||||
- 1 Patients randomized to fondaparinux sodium received an IV bolus injection of 2.5 mg followed by 2.5 mg by SC injection daily for up to 8 days or discharge.
- 2 Patients randomized to UFH received an IV bolus injection 60 IU/kg followed by an infusion of 12 IU/kg/hr for 24 to 48 hours.
- 3 The hazard ratio, fondaparinux sodium versus control, was adjusted for treatment group and strata.
4 Placebo patients did not receive unfractionated heparin as an anticoagulant.
In the management of STEMI with fondaparinux sodium, the risk of all cause mortality up to Day 180 is reported in Table 36.
Table 36 Efficacy of Fondaparinux sodium for the Prevention of Adjudicated Death (All Cause Mortality) in STEMI up to 6 months in OASIS 6 (All Randomized Patients)
| Overall | Stratum 1 | Stratum 2 | |||||||||||||
| Endpoint | Fondapariux sodium1 N=6036 | Control2 N=6056 | Hazard Ratio3 (95% CI) | Fondaparinux sodium N=2823 | Placebo4 N=2835 | Hazard Ratio3 (95% CI) | Fondaparinu x sodium N=3213 | UFH N=3221 | Hazard Ratio3 (95% CI) | ||||||
| Day 9 | 368 (6.1%) | 426 (7.0%) | 0.86 (0.75, 0.99) | 202 (7.2%) | 252 (8.9%) | 0.80 (0.66, 0.96) | 166 (5.2%) | 174 (5.4%) | 0.95 (0.77, 1.17) | ||||||
| Day 30 | 470 (7.8%) | 541 (8.9%) | 0.87 (0.77, .98)6 | 257 (9.1%) | 321 (11.3%) | 0.80 (0.68, 0.94) | 213 (6.6%) | 220 (6.8%) | 0.95 (0.79, 1.15) | ||||||
| Day 90 | 545 (9.0%) | 634 (10.5%) | 0.86 (0.76, 0.96) | 301 (10.7%) | 354 (12.5%) | 0.85 (0.73, 0.99) | 244 (7.6%) | 280 (8.7%) | 0.86 (0.72, 1.02) | ||||||
| Day 180 | 599 (9.9%) | 675 (11.1%) | 0.88 (0.79, 0.99) | 336 (11.9%) | 375 (13.2%) | 0.89 (0.77, 1.04) | 263 (8.2%) | 300 (9.3%) | 0.87 (0.73, 1.02) | ||||||
- 1 Patients randomized to fondaparinux sodium received an IV bolus injection of 2.5 mg followed by 2.5 mg by SC injection daily for up to 8 days or discharge.
- 2 Patients randomized to UFH received an IV bolus injection 60 IU/kg followed by an infusion of 12 IU/kg/hr for 24 to 48 hours.
- 3 The hazard ratio, fondaparinux sodium versus control, was adjusted for treatment group and strata.
4 Placebo patients did not receive unfractionated heparin as an anticoagulant.
The results for the primary endpoint (death or reinfarction) at Day 30 by reperfusion strategy are presented in Table 37.
Table 37 Efficacy of Fondaparinux sodium for the Prevention of Adjudicated Death or Reinfarction in STEMI up to Day 30 in OASIS 6 by Initial Reperfusion Strategy (All Randomized Patients)
| Endpoint | Fondapariux sodium (N=6036) | Control (N=6056) | Hazard Ratio (95% CI) |
| Overall (primary endpoint) | 584 (9.7%) | 675 (11.1%) | 0.86 (0.77, 0.96) 1 |
| Reperfusion Strategy | |||
| No reperfusion | 176/1452 (12.1%) | 211/1405 (15.0%) | 0.79 (0.65, 0.97) |
| Thrombolytic Agent | 295/2695 (10.9%) | 373/2742 (13.6%) | 0.79 (0.68, 0.93) |
| 50/425 (11.8%) | 54/443 (12.2%) | 0.98 (0.67, 1.44) |
| 244/2267 (10.8%) | 318/2298 (13.8%) | 0.77 (0.65, 0.90) |
| Primary PCI | 113/1889 (6.0%) | 91/1909 (4.8%) | 1.26 (0.96, 1.66) |
| Patients receiving Thrombolytics or No reperfusion2 | |||
| Overall | 471/4147 (11.4%) | 584/4147 (14.1%) | 0.80 (0.70, 0.90) |
| 318/2813 (11.3%) | 395/2828 (14.0%) | 0.80 (0.69, 0.92) |
| 153/1334 (11.5%) | 189/1319 (14.3%) | 0.79 (0.64, 0.98) |
- 1 p-value versus control: 0.008
- 2 Patients not undergoing primary PCI
- 3 UFH Not Indicated
- 4 UFH Indicated
The rates of major bleeding episodes for STEMI patients treated with fondaparinux sodium vs. control (UFH/placebo) are provided in Table 9 (see ADVERSE REACTIONS).
The results for major bleeding by initial reperfusion strategy are presented in Table 38.
Table 38 Major Bleeding in the OASIS 6 Study by Initial Reperfusion Strategy (As Treated Patients)
| Endpoint | Fondaparinux sodium | Control | Hazard Ratio (95% CI) |
| On-therapy | |||
| Overall | 99/5954 (1.7) | 120/5947 (2.0) | 0.82 (0.63, 1.07) |
| Reperfusion Strategy | |||
| No reperfusion | 16/1415 (1.1) | 24/1367 (1.8) | 0.64 (0.34, 1.20) |
| Thrombolytic Agent | 47/2676 (1.8) | 66/2711 (2.4) | 0.72 (0.49, 1.04) |
| 10/420 (2.47) | 18/443 (4.2) | 0.58 (0.27, 1.26) |
| 37/2253 (1.6) | 48/2277 (2.1) | 0.77 (0.50, 1.18) |
| Primary PCI | 36/1863 (1.9) | 30/1869 (1.6) | 1.21 (0.74, 1.96) |
| Patients receiving Thombolytics or No reperfusion1 | |||
| Overall | 63/4091 (1.5) | 90/4078 (2.2) | 0.69 (0.50, 0.95) |
| 40/2802 (1.4) | 53/2813 (1.9) | 0.75 (0.50, 1.13) |
| 23/1289 (1.8) | 37/1265 (2.9) | 0.61 (0.36, 1.02) |
| By Day 9 | |||
| Overall | 104/5954 (1.7) | 128/5947 (2.1) | 0.81 (0.62, 1.05) |
| Reperfusion Strategy | |||
| No reperfusion | 17/1415 (1.2) | 24/1367 (1.8) | 0.68 (0.36, 1.26) |
| Thrombolytic Agent | 47/2676 (1.8) | 73/2711 (2.7) | 0.65 (0.45, 0.93) |
| 10/420 (2.4) | 18/433 (4.2) | 0.58 (0.27, 1.26) |
| 37/2253 (1.6) | 55/2277 (2.4) | 0.67 (0.44, 1.01) |
| Primary PCI | 40/1863 (2.1) | 31/1869 (1.7) | 1.30 (0.81, 2.08) |
| Patients receiving Thombolytics or No reperfusion1 | |||
| Overall | 64/4091 (1.6) | 97/4078 (2.4) | 0.65 (0.47, 0.89) |
| 39/2802 (1.4) | 58/2813 (2.1) | 0.67 (0.45, 1.00) |
| 25/1289 (1.9) | 39/1265 (3.1) | 0.63 (0.38, 1.03) |
- 1 Patients not undergoing primary PCI
- 2 UFH Not Indicated
- 3 UFH Indicated
14 NON-CLINICAL TOXICOLOGY
Acute Toxicity
Single subcutaneous or intravenous doses of 40 mg/kg were well tolerated in mice, rats and monkeys. No lethal effects were observed. This dose represents up to 1200 times the recommended human dose.
Long Term Toxicity
Repeated dose toxicity studies were performed in rats and monkeys at dose levels of 0.4, 2 and
10 mg/kg/d, up to 12, 60 and 300 times the recommended human doses. Fondaparinux had low toxicity and induced mainly an increase of the trauma-related hemorrhage.
Small numbers of animal deaths were due to hemorrhage and hematomas. These were primarily attributed to repeated injection traumas and to the pharmacological activity of the compound.
In monkey studies, some large hematomas were also observed at handling sites, blood puncture and anaesthetic injection sites.
Carcinogenicity
Fondaparinux has not been tested for its carcinogenic potential in long-term animal studies.
Mutagenicity
Fondaparinux was not mutagenic in the in vitro Ames Test nor the mouse lymphoma cell (L5178Y/TK+/-) forward mutation test. Fondaparinux was not clastogenic in the human lymphocyte chromosomal aberration test, rat hepatocyte unscheduled DNA synthesis (UDS) test or in the in vivo rat micronucleus test.
Reproduction and Teratology
Fondaparinux at doses up to 10 mg/kg/day (i.e. doses up to 280 times the human daily doses) did not impair the reproduction parameters studied: rat mating performance and fertility, rat and rabbit gestation and embryo-fetal development and rat parturition, lactation, new-born viability and growth, F1 behaviour and reproduction and F2 fetal development.
The main treatment-related findings were hematomas and hemorrhage at the injection site. The only other treatment-related finding noted was one fatality associated with hematoma and changes in liver and lungs.
Very low placental transfer and very limited excretion in the milk were demonstrated in rats.
15 SUPPORTING PRODUCT MONOGRAPHS
ARIXTRA® (Solution, 2.5 mg / 0.5 mL, 5 mg / 0.4 mL, 7.5 mg / 0.6 mL and 10 mg / 0.8 mL), submission control 225665, Product Monograph, Aspen Pharmacare Canada Inc. (July 19, 2019)