


Product Monograph - Fycompa
RECENT MAJOR LABEL CHANGES
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 3
1 INDICATIONS ............................................................................................................... 3
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.3 Administration ........................................................................................................ 7
4.4 Missed Dose ........................................................................................................... 7
5 OVERDOSAGE .............................................................................................................. 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 8
7 WARNINGS AND PRECAUTIONS .................................................................................. 9
7.1 Special Populations............................................................................................... 16
7.1.1 Pregnant Women ........................................................................................... 16
7.1.2 Breast-feeding ................................................................................................ 17
7.1.3 Pediatrics ........................................................................................................ 17
7.1.4 Geriatrics ........................................................................................................ 17
8 ADVERSE REACTIONS ................................................................................................ 18
8.1 Adverse Reaction Overview .................................................................................. 18
8.2 Clinical Trial Adverse Reactions ............................................................................ 18
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................... 26
| 7 WARNINGS AND PRECAUTIONS | 11/2023 |
|---|
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 32
8.5 Post-Market Adverse Reactions ........................................................................... 33
9 DRUG INTERACTIONS ................................................................................................ 33
9.2 Drug Interactions Overview .................................................................................. 33
9.3 Drug-Behavioural Interactions .............................................................................. 33
9.4 Drug-Drug Interactions ......................................................................................... 33
9.5 Drug-Food Interactions ......................................................................................... 36
9.6 Drug-Herb Interactions ......................................................................................... 36
9.7 Drug-Laboratory Test Interactions ........................................................................ 36
10 CLINICAL PHARMACOLOGY ....................................................................................... 36
10.1 Mechanism of Action ...................................................................................... 36
10.2 Pharmacodynamics ........................................................................................ 36
10.3 Pharmacokinetics ........................................................................................... 37
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 40
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 40
PART II: SCIENTIFIC INFORMATION ....................................................................................... 40
13 PHARMACEUTICAL INFORMATION ............................................................................ 40
14 CLINICAL TRIALS ........................................................................................................ 41
14.1 Clinical Trials by Indication, Trial Design and Study Demographics ................ 41
Partial-Onset Seizures: ................................................................................................... 41
Primary Generalized Tonic-Clonic (PGTC) Seizures: ........................................................ 44
15 MICROBIOLOGY ........................................................................................................ 45
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 45
PATIENT MEDICATION INFORMATION .................................................................................. 48
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
FYCOMPA (perampanel) tablets are indicated as:
adjunctive therapy in the management of partial-onset seizures in patients 7 years of age and older
- who are not satisfactorily controlled with conventional therapy.
- adjunctive therapy in the management of primary generalized tonic-clonic (PGTC) seizures in patients 12 years of age and older with epilepsy, who are not satisfactorily controlled with conventional therapy.
1.1 Pediatrics
Pediatrics (<7 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of FYCOMPA in children under 7 years of age has not been established; therefore, Health Canada has not authorized an indication for this patient population (see 7.1.3 Pediatrics and 10.3 Pharmacokinetics, Special Populations and Conditions).
1.2 Geriatrics
Geriatrics (≥65 years of age): There is limited information on the use of FYCOMPA in patients 65 years of age and older. No dose adjustment based on age is necessary. In general, dose selection for an elderly patient should usually start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (see 7.1.4 Geriatrics; 4.2 Recommended Dose and Dosage Adjustment, Geriatrics and 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
2 CONTRAINDICATIONS
FYCOMPA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Concomitant CYP3A Enzyme-Inducing AEDs Significantly Reduce Both FYCOMPA Plasma Levels and Efficacy: Carbamazepine, oxcarbazepine and phenytoin all decrease mean FYCOMPA blood levels by approximately 50-70% and substantially decrease FYCOMPA efficacy. As there are no clinical study data for FYCOMPA doses greater than 12 mg/day, there is insufficient information to recommend dose adjustments to correct for this (see 7 WARNINGS AND PRECAUTIONS, General; 9.4 Drug-Drug Interactions and 14.1 Clinical Trials by Indication).
Serious Aggression- and Hostility-Related Adverse Events: Closely monitor patients particularly during the titration period and at higher doses. FYCOMPA should be reduced if symptoms of aggression or hostility occur and should be discontinued immediately if symptoms are severe or worsening (see 7 WARNINGS AND PRECAUTIONS, Psychiatric and 8.2 Clinical Trial Adverse Reactions).
4.2 Recommended Dose and Dosage Adjustment
In order to optimize the balance between efficacy and tolerability, FYCOMPA must always be titrated according to individual patient response.
The maximum recommended daily dose of FYCOMPA is 12 mg/day. Safety of doses higher than 12 mg/day in any age group has not been established.
Adults (≥18 years of age), Adolescents (12 to 17 years of age), and Pediatrics (7 to 11 years of age) Partial-Onset or Primary Generalized Tonic-Clonic Seizures in the Presence of Enzyme-Inducing AEDs (EI-AEDs; including carbamazapine, oxcarbazepine, phenytoin): The recommended starting dose of FYCOMPA in the presence of EI-AEDs, including carbamazepine, oxcarbazepine and phenytoin, is 4 mg/day. Based on clinical response and tolerability, the dose may be increased by
- increments of 2 mg to a maximum dose of 12 mg/day. Dose increases should occur no more frequently than at 1-week intervals.
Clinical studies revealed a lower efficacy in these patients at a given dose, compared to those not on EI-AEDs (see 14.1 Clinical Trials by Indication). This is the result of lower FYCOMPA blood levels (see 7 WARNINGS AND PRECAUTIONS, and 9 DRUG INTERACTIONS), suggesting that relatively higher doses would be needed in this patient population to achieve similar efficacy as those not on EI-AEDs. However, safety and efficacy of FYCOMPA doses higher than 12 mg/day have not been established in any age group.
When these EI-AEDs are introduced or withdrawn from a patient’s treatment regimen, patient should be closely monitored for clinical response and tolerability. Dose adjustment of FYCOMPA may be necessary. (See also 9.4 Drug-Drug Interactions and 14.1 Clinical Trials by Indication).
In the Absence of Enzyme-Inducing AEDs: Treatment with FYCOMPA should be initiated with a dose of 2 mg/day. The dose may be increased, based on clinical response and tolerability, by increments of 2 mg up to a dose of 8 mg/day. Dose increases should occur no more frequently than at 2-week intervals.
If FYCOMPA is well tolerated at 8 mg/day but clinical response is lacking, the dose may be increased by increments of 2 mg to 12 mg/day, depending upon individual clinical response and tolerability. The maximum recommended daily dose is 12 mg.
There was little difference in efficacy between 8 and 12 mg/day (see 14.1 Clinical Trials by Indication, Partial-Onset Seizures), while the proportion of patients with adverse events, including aggression/hostility-related increased with increasing dose (see 8.2 Clinical Trial Adverse Reactions).
- Pediatrics (<7 years of age): The safety and efficacy of FYCOMPA in children under 7 years of age have not been established; therefore, Health Canada has not authorized an indication for this age group (see 10.3 Pharmacokinetics, Special Populations and Conditions, Pediatrics).
- Geriatrics (≥ 65 years of age): Clinical studies of FYCOMPA did not include sufficient number of patients aged 65 and over to determine the safety and efficacy of FYCOMPA in the elderly population (see 14.1 Clinical trials by Indication). Because of increased likelihood for adverse reactions in the elderly, dosage increases during titration are recommended no more frequently than every 2 weeks (see 1.2 Geriatrics and 7.1.4 Geriatrics).
- Patients with Renal Impairment: Dose adjustment is not required in patients with mild renal impairment. Use in patients with moderate or severe renal impairment or patients undergoing hemodialysis is not recommended (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
- Patients with Hepatic Impairment: Dosage adjustment is recommended in patients with mild and moderate hepatic impairment, based on higher exposure and the longer half-life of perampanel. The maximum recommended daily dose is 6 mg for patients with mild hepatic impairment and 4 mg for patients with moderate hepatic impairment. Starting dose should be 2 mg per day with increments of 2 mg every two weeks until target dose is achieved. Dose increases in patients with mild and moderate hepatic impairment, as with all patients, should be based on clinical response and tolerability. Use in patients with severe hepatic impairment is not recommended (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
- Discontinuing FYCOMPA: When withdrawing FYCOMPA, the dose should be gradually reduced. However, due to its long-half life and subsequent slow decline in plasma concentrations, FYCOMPA can be discontinued abruptly if absolutely needed (see 7 WARNINGS AND PRECAUTIONS, General).
4.3 Administration
FYCOMPA should be taken orally once daily at bedtime.
4.4 Missed Dose
Single missed dose: As perampanel has a long half-life, the patient should wait and take their next dose as scheduled.
If more than 1 dose has been missed, for a continuous period of less than 5 half-lives (3 weeks for patients not taking perampanel metabolism-inducing anti-epileptic drugs (AED), 1 week for patients taking perampanel metabolism-inducing AEDs consideration should be given to restart treatment from the last dose level (see 9 DRUG INTERACTIONS).
If a patient has discontinued perampanel for a continuous period of more than 5 half-lives, it is recommended that initial dosing recommendations given above should be followed.
5 OVERDOSAGE
There is limited clinical experience with FYCOMPA overdose in humans. The highest reported overdose was intentional and could have resulted in a dose up to 264 mg. This patient experienced events of altered mental status, agitation and aggressive behaviour and recovered without sequelae. In general, the adverse reactions associated with overdoses were similar to the reactions at therapeutic doses, with dizziness reported most frequently.
There is no available specific antidote to the overdose reactions of FYCOMPA. General supportive care of the patient is indicated including monitoring of vital signs and observation of the clinical status of the patient. Due to its long half-life, the effects caused by FYCOMPA could be prolonged. Because of low renal clearance, special interventions such as forced diuresis, dialysis or haemoperfusion are unlikely to be of value.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
FYCOMPA (perampanel) tablets are supplied as follows:
2 mg tablet: FYCOMPA tablets 2 mg perampanel are orange, round, bi-convex, film-coated tablets debossed with “2” on one side and “Є 275” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7 tablets.
4 mg tablet: FYCOMPA tablets 4 mg perampanel are red, round, bi-convex, film-coated tablets debossed with “4” on one side and “Є 277” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7, 28, 84, and 98 tablets.
6 mg tablet: FYCOMPA tablets 6 mg perampanel are pink, round, bi-convex, film-coated tablets debossed with “6” on one side and “Є 294” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7, 28, 84, and 98 tablets.
8 mg tablet: FYCOMPA tablets 8 mg perampanel are purple, round, bi-convex, film-coated tablets debossed with “8” on one side and “Є 295” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7, 28, 84, and 98 tablets.
10 mg tablet: FYCOMPA tablets 10 mg perampanel are green, round, bi-convex, film-coated tablets debossed with “10” on one side and “Є 296” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7, 28, 84, and 98 tablets.
12 mg tablet: FYCOMPA tablets 12 mg perampanel are blue, round, bi-convex, film-coated tablets debossed with “12” on one side and “Є 297” on the other. They are supplied in HDPE bottles of 30 and 90 tablets, and as blisters (PVC/aluminum) in packs of 7, 28, 84, and 98 tablets.
FYCOMPA tablets contain the following inactive ingredients: hypromellose 2910, lactose monohydrate, low substituted hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, polyethylene glycol 8000, povidone, talc and titanium dioxide and contain the following colouring agents:
2 mg tablets: yellow ferric oxide, red ferric oxide
4 mg tablets: red ferric oxide
6 mg tablets: red ferric oxide
8 mg tablets: black ferric oxide, red ferric oxide
10 mg tablets: FD&C Blue #2 indigo carmine aluminum lake, yellow ferric oxide
12 mg tablets: FD&C Blue #2 indigo carmine aluminum lake
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength | Non-medicinal Ingredients |
| Oral | Tablets / 2 mg, 4 mg, 6 mg, 8 mg, 10 mg, and 12 mg | hypromellose, lactose monohydrate, low-substituted hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, polyethylene glycol, povidone, talc and titanium dioxide and dye pigments: 2 mg tablets: yellow ferric oxide, red ferric oxide 4 mg tablets: red ferric oxide 6 mg tablets: red ferric oxide 8 mg tablets: black ferric oxide, red ferric oxide 10 mg tablets: FD&C Blue #2 indigo carmine aluminum lake, yellow ferric oxide 12 mg tablets: FD&C Blue #2 indigo carmine aluminum lake |
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Hypersensitivity
Multi-organ Hypersensitivity Reactions: Multiorgan hypersensitivity (also known as Drug Reaction with Eosinophilia and Systemic Symptoms [DRESS]) has been reported in patients taking antiepileptic drugs, including FYCOMPA. DRESS may be fatal or life-threatening. DRESS typically, although not exclusively, presents with fever, rash, lymphadenopathy, and/or facial swelling, in association with other organ system involvement, such as hepatitis, nephritis, hematological abnormalities, myocarditis, or myositis sometimes resembling an acute viral infection. Eosinophilia is often present. Because this disorder is variable in its expression, other organ systems not noted here may be involved. It is important to note that early manifestations of hypersensitivity, such as fever or lymphadenopathy, may be present even though rash is not evident. If such signs or symptoms are present, the patient should be evaluated immediately. If an alternative etiology for the signs or symptoms cannot be established, FYCOMPA should be discontinued and other treatment options considered (see 4.2 Recommended Dose and Dosing Adjustment, Discontinuing FYCOMPA).
Substantial Decrease in Mean FYCOMPA Plasma Levels for Patients on Concomitant CYP3A Enzyme-Inducing AEDs (Carbamazepine, Oxcarbazepine, Phenytoin): Carbamazepine, oxcarbazepine, and phenytoin (all strong cytochrome P450 inducers) decrease FYCOMPA plasma concentrations and efficacy to a clinically significant extent, as compared to patients not on these AEDs (see 9.4 Drug-Drug Interactions; 14.1 Clinical Trials by Indication). The rate of occurrence of adverse events in clinical studies was often greater in the absence of concomitant enzyme-inducing AEDs (EI-AEDs), apparently reflecting higher mean FYCOMPA blood levels in that condition of use.
Inadequate Data on Maximal Effective Dosing for Patients on Concomitant CYP3A Enzyme-Inducing AEDs (Carbamazepine, Oxcarbazepine, Phenytoin): The reduction in FYCOMPA exposure per given FYCOMPA dose, for adult and adolescent patients on concomitant EI-AEDs, may result in consideration by the prescriber of higher FYCOMPA doses for these patients in order to compensate. It is important for the prescriber to be aware that the efficacy and safety outcomes of FYCOMPA doses above 12 mg/day are currently unknown because they have not been studied. The unknowns with respect to FYCOMPA doses >12 mg/day are magnified due to remaining uncertainties with FYCOMPA metabolism, including the potential for FYCOMPA to impact on the PK of other AEDs, and the potential for increased production of reactive metabolites with increasing doses of FYCOMPA.
This means that i) doses above 12 mg/day cannot be recommended for any patients; and ii) there is inadequate information about the maximum effective dose range specifically in the population of patients taking EI AEDs (see 4 DOSING AND ADMININSTRATION; 9.4 Drug-Drug Interactions, Interactions between FYCOMPA and other anti-epileptic drugs (AEDs)).
Drug Interactions: Strong CYP3A Inducers other than AEDs: Strong CYP3A inducers other than AEDs (e.g., rifampin, St. John’s wort, some antiretrovirals) may significantly decrease FYCOMPA blood levels (see 9.4 Drug-Drug Interactions).
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY, Carcinogenicity for discussion on animal data.
Dependence/Tolerance
Abuse Potential: Caution should be exercised in patients with a history of substance abuse and the patient should be monitored for symptoms of perampanel abuse (see 8.2 Clinical Trial Adverse Reactions, Drug Abuse and Dependence/Liability).
Driving and Operating Machinery
Exercise caution when driving or operating a vehicle or potentially dangerous machinery.
FYCOMPA may cause dizziness and somnolence and therefore may influence the ability to drive or use machines. Patients are advised not to drive a vehicle, operate complex machinery or engage in other potentially hazardous activities requiring mental alertness, until the effect of FYCOMPA is known.
Endocrine and Metabolism
FYCOMPA contains lactose, therefore patients with rare hereditary problems of galactose intolerance, the Lapp lactase deficiency or glucose-galactose malabsorption should not take this medicine.
Neurologic
Withdrawal of Antiepileptic Drugs (AEDs): Although perampanel has a long half-life, it may be advisable, as with all AEDs, to gradually withdraw FYCOMPA to minimise the potential of increased seizure frequency. However, due to its long-half life and subsequent slow decline in plasma concentrations, FYCOMPA can be discontinued abruptly if absolutely needed (see 4.2 Recommended Dose and Dosage Adjustment).
Hostility- and Aggression-related Events: see 3 WARNINGS AND PRECAUTIONS BOX.
Dizziness, Disturbance in Gait and Coordination and Falls: FYCOMPA caused dose-related increases in events related to dizziness, disturbance in gait or coordination, and falls. In the absence of EI-AEDs, the rate of coordination-related events at FYCOMPA doses of 8 to 12 mg/day was 54% for FYCOMPA vs 15% for placebo. In the presence of EI-AEDs, the rates were 47% and 13% respectively (see 8.2 Clinical Trial Adverse Reactions, Table 4).
These adverse reactions occurred mostly during the titration phase and led to discontinuation more frequently in FYCOMPA-treated patients than in placebo-treated. Elderly patients had an increased risk of these adverse reactions compared to younger adults and adolescents. An increased risk of falls, in some cases leading to serious injuries including head injuries and bone fracture, occurred in patients being treated with FYCOMPA (with and without concurrent seizures). In the controlled partial-onset seizure clinical studies, falls were reported in 5% and 10% of patients receiving FYCOMPA 8 and 12 mg per day, respectively (Placebo: 3%).
Somnolence- and Fatigue- Related Events: FYCOMPA caused dose-dependent increases in somnolence and fatigue-related events (including fatigue, asthenia, and lethargy). In the absence of EI-AEDs, the rate of somnolence/fatigue-related events at FYCOMPA doses of 8 to 12 mg/day was 39% for FYCOMPA vs 11% for placebo. In the presence of EI-AEDs, the rates were 24% and 13% respectively (see 8.2 Clinical Trial Adverse Reactions, Table 4).
These adverse reactions occurred mostly during the titration phase and led to discontinuation more frequently in FYCOMPA-treated patients than placebo-treated patients. Elderly patients had an increased risk of these adverse reactions compared to younger adults and adolescents.
Ophthalmologic
In controlled Phase 3 clinical studies, FYCOMPA treatment was associated with vision-related adverse events primarily in the population of patients taking EI-AEDs, with an apparent dose-relatedness (see 8.2 Clinical Trial Adverse Reactions, Table 2 and Table 3). In this patient population, diplopia was reported at a rate of 5% in the FYCOMPA 12 mg/day arm, compared to 2% at lower doses, and 1% in the placebo arm. Blurred vision was reported at a rate of 5% in the 12 mg/day arm, compared to 4% and 0 in the 8 and 4 mg/day arms respectively, and 2% in placebo. Out of all patients randomized to FYCOMPA, 4 patients (0.4%) discontinued treatment due to vision-related adverse events (each for diplopia).
Psychiatric
Clinical Trial Data Related to Serious Psychiatric and Behavioural Reactions: In general, in placebo-controlled Phase 3 epilepsy studies, neuropsychiatric events were reported more frequently in patients taking FYCOMPA than in patients taking placebo. This is true in both the presence and absence of concomitant enzyme-inducing AEDs (EI-AEDs), but not unexpectedly, the rates are lower in the presence of EI-AEDs, apparently reflecting the lower mean FYCOMPA blood levels (see 8.2 Clinical Trial Adverse Reactions, Table 2 and Table 3).
Neuropsychiatric Events - Aggression and Hostility-related:
Adults (≥ 18 years of age): In the absence of enzyme-inducing AEDS (EI-AEDs), the rate of aggression- and hostility-related events at FYCOMPA doses of 8 to 12 mg/day, in the three phase 3 POS studies 304, 305, and 306, was 21% for FYCOMPA vs 8% for placebo. In the presence of EI- AEDs, the rates were 10% and 4% respectively (see 8.2 Clinical Trial Adverse Reactions, Table 4). These events included irritability, belligerence, affect lability, agitation, mood swings, frustration, anger, and physical assault. FYCOMPA-treated patients experienced more hostility- and aggression-related adverse reactions that were serious, severe, or life-threatening and led to dose reduction, interruption, and discontinuation more frequently than placebo-treated patients. These effects were dose-related and generally appeared within the first 6 weeks of treatment, although new events continued to be observed through more than 37 weeks. Six patients out of 4,368 perampanel-treated patients exhibited homicidal ideation or threat in controlled and open-label studies, including non-epilepsy studies.
In the Phase 3 epilepsy studies these events occurred in patients with and without prior psychiatric history, prior aggressive behaviour, or concomitant use of medications associated with hostility and aggression. Some patients experienced worsening of their pre-existing psychiatric conditions.
Patients with documented active psychotic disorders and unstable recurrent affective disorders were excluded from the clinical studies. The combination of alcohol and FYCOMPA significantly worsened mood and increased anger (see 9.4 Drug-Drug Interactions, Alcohol and Other CNS Depressants). Patients taking FYCOMPA should avoid the use of alcohol.
In healthy volunteers taking FYCOMPA, observed psychiatric events included paranoia, euphoric mood, agitation, anger, mental status changes, and disorientation/confusional state. In the non-epilepsy trials, psychiatric events that occurred in FYCOMPA-treated subjects more often than placebo-treated subjects included disorientation, delusion, and paranoia.
Adolescents (12-17 years of age): In adolescents receiving FYCOMPA doses of 8 to 12 mg/day, both with and without EI-AEDs, the total combined incidence rates across five Phase 3 placebo-controlled adjunctive studies in the adverse event category of aggression or hostility were 18.1%, compared with 7.6% for placebo. Events in this category included aggression, irritability, skin laceration, abnormal behaviour, anger, agitation, paranoia, personality disorder, and physical abuse (see 8.2.1 Clinical Trial Adverse Reactions – Pediatrics, Table 7).
Aggression was observed more frequently in adolescents than in adults (9.1% in the adolescent population compared with 1.2% in the adult population) across doses of 4mg/day to 12mg/day, in the three Phase 3 double-blind studies; In the PGTCs study, aggression was reported at a rate of 1.5% in the adult population and was not reported in the adolescent population.
Across the five controlled studies in partial-onset seizures and PGTCs, aggression was observed more frequently in adolescent patients in the absence of EI-AEDs (8.9%) than in adolescent patients taking enzyme inducing concomitant AEDs (3.6%).
Children (7 - 11 years of age): In children 7-11 years of age receiving FYCOMPA across all doses, both with and without EI-AEDs, the total combined incidence rates in the adverse event category of aggression or hostility were 27.5%. Events in this category include irritability, aggression, agitation, psychomotor hyperactivity, anger, affect lability, defiant behaviour, disruptive mood dysregulation disorder, mood altered, and oppositional defiant disorder.
Aggression was observed frequently (8.3%) in children aged 7-11 years across all doses compared to adolescents (9.1%) and adults (1.2%) across doses of 4 mg/day to 12 mg/day (see 8.2.1 Clinical Trial Adverse Reactions – Pediatrics, Table 6).
Recommendations to the Health-care Professional: Patients, their caregivers, and families should be informed that FYCOMPA may increase the risk of psychiatric events. They should be informed to avoid alcohol. Patients should be monitored during treatment and for at least one month after the last dose of FYCOMPA, and especially when taking higher doses and during the initial few weeks of drug therapy (titration period) or at other times of dose increases. Dose of FYCOMPA should be reduced if these symptoms occur. Permanently discontinue FYCOMPA for persistent severe or worsening psychiatric symptoms or behaviours and refer for psychiatric evaluation (see 4.2 Recommended Dose and Dosage Adjustment, Discontinuing FYCOMPA and 7 WARNINGS AND PRECAUTIONS, Patient Counselling Information).
Suicidal Ideation and Behaviour: Suicidal ideation and behaviour have been reported in patients treated with antiepileptic agents in several indications.
All patients treated with antiepileptic drugs (AEDs), irrespective of indication, should be monitored for signs of suicidal ideation and behaviour and appropriate treatment should be considered. Patients (and caregivers of patients) should be advised to seek medical advice should signs of suicidal ideation or behaviour emerge.
An FDA meta-analysis of randomized placebo-controlled trials, in which AEDs were used for various indications, has shown a small increased risk of suicidal ideation and behaviour in patients treated with these drugs. The mechanism of this risk is not known.
There were 43,892 patients treated in the placebo controlled clinical trials that were included in the meta-analysis. Approximately 75% of patients in these clinical trials were treated for indications other than epilepsy and, for the majority of non-epilepsy indications the treatment (AED or placebo) was administered as monotherapy. Patients with epilepsy represented approximately 25% of the total number of patients treated in the placebo controlled clinical trials and, for the majority of epilepsy patients, treatment (AED or placebo) was administered as adjunct to other antiepileptic agents (i.e., patients in both treatment arms were being treated with one or more AED). Therefore, the small increased risk of suicidal ideation and behaviour reported from the meta-analysis (0.43% for patients on AEDs compared to 0.24% for patients on placebo) is based largely on patients that received monotherapy treatment (AED or placebo) for non-epilepsy indications. The study design does not allow an estimation of the risk of suicidal ideation and behaviour for patients with epilepsy that are taking AEDs, due both to this population being the minority in the study, and the drug-placebo comparison in this population being confounded by the presence of adjunct AED treatment in both arms.
Reproductive Health: Female and Male Potential
For information on developmental toxicity, see 7.1 Special Populations, 7.1.1 Pregnant Women, 7.1.2 Breast-feeding, 7.1.3 Pediatrics and 16 NON-CLINICAL TOXICOLOGY.
- Women of Childbearing Potential and Hormonal Contraceptives
Use of FYCOMPA with oral contraceptives containing levonorgestrel has been shown to decrease mean levonorgestrel exposure by approximately 40%. Therefore, use with FYCOMPA with oral or implant contraceptives may render them less effective and an additional reliable non-hormonal method (intra-uterine device (IUD), condom) is to be used (see 9.4 Drug-Drug Interactions, Oral Contraceptives).
- Fertility
No human data on the effects of FYCOMPA on fertility are available (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Patient Counselling Information
A Consumer Information sheet should be provided when FYCOMPA tablets are dispensed to the patient. Patients receiving FYCOMPA should be given the following instructions by the physician:
Serious Psychiatric and Behavioural Reactions, including Hostility and Aggression
Counsel patients, families and caregivers of the need to monitor for the emergence of anger, aggression, hostility, unusual changes in mood, personality, or behaviour, and other behavioural symptoms. Instruct patients, caregivers and families to report behaviours of concern immediately to healthcare providers.
Suicidal Thinking and Behaviour
Counsel patients, their caregivers, and families that AEDs, including FYCOMPA, may increase the risk of suicidal thinking and behaviour and advise them of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behaviour, or the emergence of suicidal thoughts, behaviour, or thoughts about self-harm. Instruct patients, caregivers and families to report behaviours of concern immediately to healthcare providers.
Dizziness, Gait Disturbance, Somnolence, Fatigue and Falls
Counsel patients that FYCOMPA may cause dizziness, gait disturbance, somnolence, and fatigue. Advise patients taking FYCOMPA not to drive, operate complex machinery, or engage in other hazardous activities until they have become accustomed to any such effects associated with FYCOMPA. Counsel patients that FYCOMPA may cause falls and injuries.
Missed Doses
Counsel patients that if they miss a dose, they should resume dosing the following day at their prescribed daily dose. Instruct patients to contact their physician if more than one day of dosing is missed.
Withdrawal of Antiepileptic Drugs
Counsel patients that abrupt discontinuation of FYCOMPA may increase seizure frequency.
Alcohol and Other CNS Depressants
Counsel patients to avoid the use of alcohol with FYCOMPA, as this combination significantly worsened mood and increased anger in clinical studies. These effects may also be seen if FYCOMPA is taken with other CNS depressants.
Contraceptives
Counsel patients that FYCOMPA may decrease efficacy of contraceptives containing levonorgestrel.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women. In animal studies, perampanel induced developmental toxicity in pregnant rat and rabbit at clinically relevant exposures (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Since the potential risk for humans is unknown, FYCOMPA should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus (see 16 NON-CLINICAL TOXICOLOGY).
If women decide to become pregnant while taking FYCOMPA, the use of this product should be carefully re-evaluated.
Labour and Delivery: The effects of FYCOMPA on labour and delivery in pregnant women are not known.
Pregnancy Registry: To provide information regarding the effects of in utero exposure to FYCOMPA, physicians are advised to recommend that pregnant patients taking FYCOMPA enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves. Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/.
7.1.2 Breast-feeding
Studies in lactating rats have shown that perampanel and/or its metabolites are excreted in milk and can cause developmental toxicity in the offspring. It is not known whether FYCOMPA is excreted in human milk. Because of the potential for serious adverse reactions in nursing infants from FYCOMPA, a decision should be made whether to discontinue nursing or discontinue FYCOMPA. FYCOMPA should only be used during lactation when benefits outweigh risks (see 16 NON-CLINICAL TOXICOLOGY).
7.1.3 Pediatrics
Pediatrics (7-11 years of age): The efficacy of FYCOMPA has been evaluated in children 7 years of age and older using an extrapolation approach based on data from previous studies of FYCOMPA in adults and adolescents with partial-onset seizures, and pharmacokinetic data from adult, adolescent and pediatric patients. The extrapolation approach was based on achieving similar systemic exposure of FYCOMPA in this patient population compared to adults taking recommended doses.
The safety of FYCOMPA in patients between 7-11 years of age was established based on data from two open-label, uncontrolled clinical studies in which a total of 162 patients contributed to safety. Of these, 117 patients between 7-11 years of age were exposed to FYCOMPA, for at least 6 months and 30 patients for longer than 12 months (see 8.2.1 Clinical Trial Adverse Reactions – Pediatrics; 10.3 Pharmacokinetics, Special Populations and Conditions, Pediatrics, and 14.1 Clinical Trials by Indication).
Pediatrics (<7 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of FYCOMPA in pediatric patients under 7 years of age have not been established; therefore, Health Canada has not authorized an indication for this patient population.
7.1.4 Geriatrics
Geriatrics (≥65 years of age):
Clinical studies of FYCOMPA did not include sufficient numbers of patients aged 65 and over (n= 28) to determine whether they respond differently than younger patients. Elderly patients may be at increased risk of central nervous system events. Caution should be exercised during dose titration (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics, 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
In all controlled and uncontrolled studies in adult and adolescent patients with partial-onset seizures, 1639 patients have received perampanel, of whom 1174 have been treated for 6 months and 703 for longer than 12 months.
In the controlled study and open-label extension in patients with primary generalized tonic-clonic seizures (PGTC), 114 patients have received FYCOMPA, of whom 68 have been treated for 6 months and 36 for longer than 12 months.
In controlled Phase 3 partial-onset clinical studies, adverse reactions reported in ≥ 5% of patients treated with FYCOMPA (perampanel) were dizziness, somnolence, fatigue, irritability, nausea, ataxia, and fall. Most events in all treatment groups were considered mild or moderate.
The adverse event profile for the PGTC clinical study was similar to that of the partial-onset studies.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Partial-Onset Seizures and Primary Generalized Tonic-Clonic Seizures in Adults:
The partial-onset data are also representative of the PGTC adverse event findings in both adults and adolescents.
Table 1 and Table 2 together provide the incidence of treatment-emergent adverse events that occurred in ≥2% of adult patients with partial-onset seizures in three Phase 3 controlled adjunctive studies (n = 780 total randomized to FYCOMPA 4 to 12 mg/day plus other AEDs and for which the frequency was greater than placebo (n=397). Table 2 presents the events that occurred in the absence of concomitant enzyme-inducing AEDs (EI-AEDs), while Table 3 presents the events that occurred in the presence of EI-AEDS (i.e., carbamazepine, oxcarbazepine, phenytoin).
Table 2: Treatment-Emergent Adverse Event Incidence in the Absence of Enzyme-Inducing Concomitant AEDs, in three Phase 3 Placebo-Controlled Adjunctive Studies in Adult Patients with Partial-Onset Seizures (Events ≥ 2% of patients in the FYCOMPA 12 mg arm and numerically more frequent than placebo) (Patients ≥18 Years)
| System Organ Class/ Preferred Term | Placebo n=170 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=71 % | 8 mg n=156 % | 12 mg n=85 % | ||
| Ear and Labyrinth Disorders | ||||
| Vertigo | 1 | 6 | 3 | 5 |
| Eye Disorders | ||||
| Vision blurred | 1 | 3 | 3 | 4 |
| Gastrointestinal Disorders | ||||
| Diarrhea | 4 | 4 | 5 | 5 |
| Nausea | 4 | 4 | 8 | 11 |
| Paresthesia oral | 0 | 0 | 0 | 2 |
| Vomiting | 3 | 4 | 3 | 6 |
| Infections and Infestations | ||||
| Pharyngitis | 1 | 0 | 0 | 4 |
| Upper respiratory tract infection | 2 | 3 | 3 | 5 |
| Injury, Poisoning and Procedural Complications | ||||
| Chest injury | 0 | 0 | 0 | 2 |
| Contusion | 2 | 0 | 4 | 6 |
| Excoriation | 1 | 1 | 2 | 2 |
| Falls | 4 | 1 | 4 | 18 |
| Hand fracture | 0 | 0 | 1 | 4 |
| Head injury | 1 | 0 | 1 | 2 |
| Joint sprain | 1 | 0 | 1 | 2 |
| Scratch | 0 | 0 | 0 | 2 |
| Skin laceration | 1 | 0 | 2 | 6 |
| System Organ Class/ Preferred Term | Placebo n=170 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=71 % | 8 mg n=156 % | 12 mg n=85 % | ||
| Investigations | ||||
| Weight gain | 1 | 9 | 3 | 6 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Arthralgia | 2 | 0 | 3 | 5 |
| Back pain | 2 | 1 | 1 | 7 |
| Musculoskeletal pain | 1 | 1 | 1 | 5 |
| Myalgia | 2 | 0 | 2 | 5 |
| Pain in extremity | 1 | 0 | 4 | 6 |
| Peripheral edema | 0 | 1 | 1 | 4 |
| Nervous System Disorders | ||||
| Asthenia | 1 | 1 | 2 | 2 |
| Ataxia | 0 | 1 | 6 | 15 |
| Aphasia | 1 | 0 | 1 | 2 |
| Balance disorder | 1 | 0 | 6 | 5 |
| Convulsion | 3 | 0 | 2 | 4 |
| Coordination abnormal | 0 | 1 | 1 | 2 |
| Dizziness | 10 | 13 | 31 | 48 |
| Dysarthria | 0 | 0 | 6 | 7 |
| Fatigue | 4 | 9 | 13 | 20 |
| Gait disturbance | 2 | 0 | 10 | 4 |
| Hypoaesthesia | 1 | 0 | 0 | 2 |
| Lethargy | 1 | 0 | 0 | 2 |
| Memory impairment | 1 | 0 | 1 | 2 |
| Paresthesia | 0 | 0 | 1 | 4 |
| Somnolence | 7 | 7 | 20 | 21 |
| Psychiatric Disorders | ||||
| Aggression | 1 | 0 | 1 | 2 |
| Anger | 1 | 0 | 0 | 7 |
| System Organ Class/ Preferred Term | Placebo n=170 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=71 % | 8 mg n=156 % | 12 mg n=85 % | ||
| Anxiety | 1 | 3 | 2 | 2 |
| Confusional state | 0 | 0 | 1 | 2 |
| Depression | 1 | 0 | 1 | 5 |
| Euphoric mood | 0 | 0 | 0 | 2 |
| Insomnia | 7 | 0 | 5 | 9 |
| Irritability | 5 | 3 | 10 | 15 |
| Renal and Urinary Disorders | ||||
| Haematuria | 0 | 0 | 0 | 2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Cough | 2 | 1 | 1 | 5 |
| Oropharyngeal pain | 1 | 4 | 1 | 4 |
| Rhinorrhoea | 2 | 0 | 1 | 4 |
| Epistaxis | 0 | 0 | 1 | 4 |
Table 3: Treatment-Emergent Adverse Event Incidence in the Presence of Enzyme-Inducing Concomitant AEDs (i.e., Carbamazepine, Oxcarbazepine, Phenytoin), in three Phase 3 Placebo-Controlled Adjunctive Studies in Adult Patients with Partial-Onset Seizures (Events ≥ 2% of patients in the FYCOMPA 12 mg arm and numerically more frequent than placebo) (Patients ≥18 Years)
| System Organ Class/ Preferred Term | Placebo n=227 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=88 % | 8 mg n=230 % | 12 mg n=150 % | ||
| Ear and Labyrinth Disorders | ||||
| Vertigo | 1 | 2 | 4 | 5 |
| Eye Disorders | ||||
| Diplopia | 1 | 2 | 2 | 5 |
| Vision blurred | 2 | 0 | 4 | 5 |
| Gastrointestinal Disorders | ||||
| Abdominal pain | 2 | 1 | 2 | 3 |
| System Organ Class/ Preferred Term | Placebo n=227 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=88 % | 8 mg n=230 % | 12 mg n=150 % | ||
| Nausea | 5 | 1 | 4 | 7 |
| Infections and Infestations | ||||
| Nasopharyngitis | 4 | 1 | 4 | 5 |
| Injury, Poisoning and Procedural Complications | ||||
| Falls | 3 | 2 | 6 | 7 |
| Head injury | 2 | 1 | 1 | 3 |
| Investigations | ||||
| Gamma-Glutamyltransferase increased | <1 | 0 | 1 | 2 |
| Weight increased | 1 | 1 | 5 | 4 |
| Metabolism and Nutrition Disorders | ||||
| Hyponatraemia | <1 | 0 | 0 | 3 |
| Musculoskeletal and Connective Tissue Disorders | ||||
| Back pain | 2 | 2 | 2 | 4 |
| Myalgia | 2 | 1 | 1 | 3 |
| Nervous System Disorders | ||||
| Asthenia | <1 | 0 | 2 | 2 |
| Ataxia | 0 | 0 | 1 | 5 |
| Balance disorder | <1 | 0 | 5 | 3 |
| Dizziness | 8 | 21 | 33 | 42 |
| Dysarthria | 0 | 2 | 1 | 2 |
| Fatigue | 4 | 8 | 7 | 9 |
| Gait disturbance | 1 | 2 | 1 | 4 |
| Headache | 10 | 13 | 10 | 15 |
| Hypersomnia | 0 | 1 | 1 | 3 |
| Hypoaesthesia | <1 | 0 | 0 | 3 |
| Memory impairment | 1 | 0 | 1 | 2 |
| Paresthesia | 1 | 0 | <1 | 2 |
| System Organ Class/ Preferred Term | Placebo n=227 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=88 % | 8 mg n=230 % | 12 mg n=150 % | ||
| Somnolence | 8 | 11 | 13 | 15 |
| Psychiatric Disorders | ||||
| Aggression | 0 | 0 | 1 | 2 |
| Anxiety | 1 | 1 | 4 | 5 |
| Irritability | 1 | 6 | 4 | 11 |
| Mood altered | <1 | 0 | <1 | 2 |
| Respiratory, Thoracic and Mediastinal Disorders | ||||
| Cough | 2 | 0 | 1 | 3 |
| Oropharyngeal pain | 1 | 1 | 1 | 2 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Rash | 2 | 3 | 4 | 3 |
Central Nervous System Adverse Events: FYCOMPA use is associated with the occurrence of central nervous system (CNS) adverse events; the most significant of these can be classified into the following categories:
- 1) aggression- and hostility-related events;
- 2) somnolence and fatigue; and
- 3) coordination difficulties, dizziness and falls
Table 4: Total Combined Incidence Rate at Higher Doses of FYCOMPA (8 to 12 mg) for Each of the Three Categories of CNS Adverse Events in the Absence or Presence of Enzyme-Inducing Concomitant AEDs in Phase 3 Placebo-Controlled Adjunctive Studies in Patients with Partial-Onset Seizures (Patients ≥18 Years)
| Absence of Enzyme-Inducing Concomitant AEDs | ||
|---|---|---|
| Category of CNS Adverse Events | Placebo + AED Therapy (N=187) | FYCOMPA 8-12 mg/day + AED Therapy (N=273) |
| Aggression- and Hostility- related* | 8% | 21% |
| Falls, Dizziness and Coordination Difficulties** | 15% | 54% |
| Somnolence & Fatigue*** | 11% | 39% |
| Presence of Enzyme-Inducing Concomitant AEDs | ||
| Category of CNS Adverse Events | Placebo + AED Therapy (N=255) | FYCOMPA 8-12 mg/day + AED Therapy (N=412) |
| Aggression- and Hostility- related* | 4% | 10% |
| Falls, Dizziness and Coordination Difficulties** | 13% | 47% |
| Somnolence & Fatigue*** | 13% | 24% |
* “Aggression- and hostility- related adverse events” encompasses the following terms, with verification via narratives as required: irritability, aggression, anger, mood swings, mood altered, agitation, abnormal behaviour, affect lability, affective disorder, hostility, emotional disorder, personality change, psychotic disorder, belligerence, frustration, impulse-control disorder, personality disorder, hostility, homicidal ideation ** “Falls, Dizziness and Coordination Difficulties” encompasses the following terms, with verification via narratives as required: dizziness, fall, vertigo, ataxia, gait disturbance, balance disorder, feeling drunk, motion sickness, coordination abnormal, cerebellar syndrome (plus various injuries/ fractures if due to falls, to be listed under “fall”) *** “Somnolence and Fatigue” encompasses the following terms with verification via narratives as required: somnolence, fatigue, asthenia, hypersomnia, sleep disorder, lethargy, sedation | ||
Adverse Reactions Leading to Discontinuation: In controlled Phase 3 partial-onset seizures studies in adult and adolescent patients, the rate of discontinuation as a result of an adverse event was 3%, 8 % and 19 % in patients randomized to receive FYCOMPA at the recommended doses of 4 mg, 8 mg and 12 mg/day, respectively, and 5 % in patients randomized to receive placebo.
In controlled Phase 3 partial-onset seizures studies, the three most common events leading to discontinuation were dizziness, somnolence, and fatigue. At higher doses, the adverse events most commonly leading to discontinuation (≥1% in the 8 mg or 12 mg FYCOMPA group and greater than placebo) were dizziness, somnolence, vertigo, aggression, anger, ataxia, blurred vision, irritability, and dysarthria.
Weight Gain: Weight gain has been observed with FYCOMPA use in adults.
In the Phase 3 studies of partial-onset seizures, the percentages of adults who gained at least 7% and 15% of their baseline body weight in FYCOMPA-treated patients were: 9% and 1%, respectively, as compared to 5% and 0.2% of placebo-treated patients. The frequencies are similar for the study of primary generalized tonic-clonic seizures. Clinical monitoring of weight is recommended.
Comparison of Gender and Race: No significant gender differences were noted in the incidence of adverse events. Although there were few non-Caucasian patients, no differences in the incidences of adverse events compared to Caucasian patients were observed (see 10.3 Pharmacokinetics, Special Populations).
Drug Abuse and Dependence/Liability: The human abuse potential of single oral doses of FYCOMPA (8 mg, 24 mg, and 36 mg) were compared to alprazolam C-IV (1.5 mg and 3 mg), and oral ketamine C-III (100 mg) in a study with recreational polydrug users. Supra-therapeutic doses of FYCOMPA 24 and 36 mg produced responses for “Euphoria” that were similar to ketamine 100 mg and alprazolam 3 mg. “Drug Liking”, “Overall Drug Liking”, and “Take Drug Again” for FYCOMPA were each statistically lower than ketamine 100mg. In addition, for “Bad Drug Effects”, FYCOMPA 24 mg and 36 mg produced responses significantly higher than ketamine 100mg. For “Sedation,” FYCOMPA 24 mg and 36 mg produced responses similar to alprazolam 3 mg and higher than ketamine 100 mg (see 7 WARNINGS AND PRECAUTIONS, Dependence/Tolerance).
Additionally, on VAS measures related to dissociative phenomena such as “Floating”, “Spaced Out” and “Detached,” FYCOMPA at supra-therapeutic doses produced responses similar to ketamine 100 mg and greater than both doses of alprazolam tested. Of note, due to somnolence a number of subjects had missing data around Tmax of FYCOMPA. The above described data might represent an underestimate of FYCOMPA’s effects. The duration of effects of higher doses of FYCOMPA on the majority of measures was much greater than alprazolam 3 mg and ketamine 100 mg.
In this study, the incidence of euphoria as an adverse event following FYCOMPA administration 8 mg, 24 mg and 36 mg was 37% (14/38), 46% (17/37), 46% (17/37), respectively, which was higher than alprazolam 3 mg (13%) but lower than ketamine 100 mg (89%).
Physical and Psychological Dependence: The potential for FYCOMPA to produce withdrawal symptoms has not been adequately evaluated. Data from 92 (6.2%) patients in double-blind clinical studies of partial-onset seizures and 182 (14.9%) from open-label studies suggests that abrupt termination of FYCOMPA produced no signs or symptoms that are associated with a withdrawal syndrome indicative of physical dependence. Due to the ability of perampanel to produce euphoria-type adverse events in humans, psychological dependence cannot be excluded.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Partial-Onset Seizures and Primary Generalized Tonic-Clonic Seizures: The partial-onset data are also representative of the PGTC adverse event findings in both adults and adolescents (12 to 17 years)
Adolescents (12 to 17 years):
Table 5 provides the incidence of treatment-emergent adverse events that occurred in ≥2% of adolescent patients with partial-onset seizures and primary generalized tonic-clonic seizures in the five Phase 3 controlled adjunctive studies (n = 152 total randomized to FYCOMPA 4 to 12 mg/day plus other AEDs), for which the frequency was greater than placebo (n=66).
Table 5: Treatment-Emergent Adverse Event Incidence in Phase 3 Placebo-Controlled Adjunctive Studies in Adolescent Patients (Patients 12 to 17 Years of Age) with Partial-Onset Seizures and Primary Generalized Tonic-Clonic Seizures (Events ≥ 2% of patients in the FYCOMPA 12 mg arm and numerically more frequent than placebo).
| System Organ Class/ Preferred Term | Placebo n=66 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=36 % | 8 mg n=82 % | 12 mg n=34 % | ||
| Blood and Lymphatic System Disorders | ||||
| Leukopenia | 0 | 0 | 0 | 3 |
| Eye Disorders | ||||
| Metamorphopsia | 0 | 0 | 0 | 3 |
| Gastrointestinal Disorders | ||||
| Abdominal discomfort | 0 | 0 | 0 | 3 |
| Constipation | 0 | 0 | 1 | 3 |
| Defecation urgency | 0 | 0 | 0 | 3 |
| Lip hematoma | 0 | 0 | 0 | 3 |
| Toothache | 0 | 0 | 4 | 3 |
| General Disorders and Administration Site Conditions | ||||
| Asthenia | 0 | 0 | 4 | 6 |
| Gait disturbance | 0 | 0 | 1 | 6 |
| Pyrexia | 2 | 3 | 6 | 6 |
| Infections and Infestations | ||||
| Bacterial infection | 0 | 0 | 0 | 3 |
| Influenza | 2 | 3 | 2 | 6 |
| Pharyngitis streptococcal | 0 | 0 | 0 | 3 |
| Sinusitis | 0 | 0 | 0 | 3 |
| Upper respiratory tract infection | 0 | 8 | 6 | 15 |
| Urinary tract infection | 0 | 3 | 0 | 3 |
| System Organ Class/ Preferred Term | Placebo n=66 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=36 % | 8 mg n=82 % | 12 mg n=34 % | ||
| Injury, poisoning and procedural complications | ||||
| Animal bite | 0 | 0 | 0 | 3 |
| Joint sprain | 0 | 0 | 1 | 3 |
| Limb Injury | 0 | 0 | 2 | 6 |
| Investigations | ||||
| Alanine aminotransferase increased | 0 | 0 | 0 | 3 |
| Aspartate aminotransferase increased | 0 | 0 | 0 | 3 |
| Blood creatine phosphokinase increased | 2 | 8 | 0 | 6 |
| Blood triglycerides increased | 0 | 0 | 0 | 3 |
| Weight increased | 2 | 6 | 4 | 6 |
| Metabolism and Nutrition Disorders | ||||
| Decreased appetite | 2 | 0 | 5 | 12 |
| Nervous System Disorders | ||||
| Dizziness | 8 | 22 | 20 | 30 |
| Drooling | 0 | 0 | 1 | 6 |
| Hypersomnia | 0 | 0 | 2 | 3 |
| Migraine | 0 | 0 | 0 | 3 |
| Somnolence | 6 | 11 | 13 | 30 |
| Speech disorder | 0 | 0 | 0 | 3 |
| Psychiatric disorders | ||||
| Abnormal behaviour | 0 | 0 | 1 | 3 |
| Aggression | 0 | 3 | 6 | 12 |
| Euphoric mood | 0 | 0 | 0 | 3 |
| Insomnia | 0 | 0 | 4 | 3 |
| Personality disorder | 0 | 0 | 0 | 3 |
| Renal and Urinary Disorders | ||||
| Pollakiuria | 0 | 0 | 0 | 3 |
| System Organ Class/ Preferred Term | Placebo n=66 % | FYCOMPA | ||
|---|---|---|---|---|
4 mg n=36 % | 8 mg n=82 % | 12 mg n=34 % | ||
| Reproductive System and Breast Disorders | ||||
| Hypomenorrhea | 0 | 0 | 0 | 3 |
| Ovarian mass | 0 | 0 | 0 | 3 |
| Ovarian rupture | 0 | 0 | 0 | 3 |
| Respirator, Thoracic and Mediastinal Disorders | ||||
| Productive cough | 0 | 0 | 0 | 3 |
| Skin and Subcutaneous Tissue Disorders | ||||
| Acne | 0 | 0 | 1 | 3 |
| Heat rash | 0 | 3 | 0 | 3 |
| Hyperhidrosis | 0 | 0 | 0 | 3 |
The adverse event profiles for adolescents in the pool of the five Phase 3 controlled adjunctive studies were similar in the absence and presence of concomitant EI-AEDS, across doses of 4mg/day to 12mg/day. Somnolence and aggression were reported at a higher rate in the absence of EI-AEDs than in the presence of EI-AEDs (somnolence 18.9% vs. 13.3%; aggression: 8.9% vs. 3.6%, respectively).
Central Nervous System Adverse Events in Patients 12 to 17 Years of Age:
Table 6: Total Combined Incidence Rate at Higher Doses of FYCOMPA (8 to 12 mg) for Each of Three Categories of CNS Adverse Events in five Phase 3 Placebo-Controlled Adjunctive Studies in Patients with Partial-Onset Seizures or Primary Generalized Tonic-Clonic Seizures (Patients 12 to 17 Years)
| Category of CNS Adverse Events | Placebo + AED Therapy (N= 66) | FYCOMPA 8-12 mg/day + AED Therapy (N= 116) |
|---|---|---|
| Falls, Dizziness and Coordination Difficulties* | 15.2% | 31.9% |
| Somnolence & Fatigue** | 12.1% | 29.3% |
| Category of CNS Adverse Events | Placebo + AED Therapy (N= 66) | FYCOMPA 8-12 mg/day + AED Therapy (N= 116) |
|---|---|---|
| Aggression or Hostility-related*** | 7.6% | 18.1% |
| Psychoses or Psychotic Disorders**** | 4.5% | 3.5% |
* “Falls, Dizziness and Coordination Difficulties” encompasses the following terms: dizziness, fall, vertigo, ataxia, gait disturbance, balance disorder, feeling drunk, motion sickness, coordination abnormal, cerebellar syndrome ** “Somnolence and Fatigue” encompasses the following terms: somnolence, fatigue, asthenia, hypersomnia, sleep disorder, lethargy, sedation ***“Aggression or Hostility-related adverse events”: encompasses the following terms: aggression, irritability, skin laceration, abnormal behaviour, anger, agitation, paranoia, personality disorder, physical abuse ****“Psychoses or Psychotic Disorders”: encompasses the following terms: abnormal behaviour, hallucination, paranoia, speech disorder, apathy, hallucination-visual | ||
Pediatrics (7 to 11 Years of Age): The safety of FYCOMPA in patients between 7-11 years of age was established based on data from two open-label, uncontrolled clinical studies in a total of 162 patients. Of these, 117 patients received FYCOMPA adjunctive treatment for at least 6 months and 30 for longer than 12 months. No new adverse drug reactions were identified in these trials.
In the multicenter, open-label single-arm study (Study 311) in patients 7-11 years of age with inadequately controlled partial-onset seizures (n=109), treatment-emergent adverse events that occurred in at least 5% of the patients are presented in Table 7.
Table 7: Treatment-Emergent Adverse Event Incidence in the Phase 3 Multicenter, Open-Label Uncontrolled Study 311 in Pediatric Patients (Patients 7 to 11 Years of Age) with Partial-Onset Seizures (Events ≥ 5% of Patients on FYCOMPA).
| System Organ Class/ Preferred Term | FYCOMPA n=109 % |
|---|---|
| Gastrointestinal Disorders | |
| Vomiting | 10 |
| General Disorders and Administration Site Conditions | |
| Fatigue | 6 |
| Pyrexia | 10 |
| Infections and Infestations | |
| Bronchitis | 6 |
| Gastroenteritis | 6 |
| Influenza | 10 |
| Nasopharyngitis | 20 |
| Upper respiratory tract infection | 6 |
| Nervous System Disorders | |
| Dizziness | 12 |
| Headache | 7 |
| Somnolence | 24 |
| Psychiatric disorders | |
| Aggression | 8 |
| Agitation | 6 |
| Irritability | 9 |
The adverse event profiles for pediatric patients were similar in the absence and presence of concomitant EI-AEDS, except for somnolence, influenza, irritability, aggression, and bronchitis which occurred at a higher frequency in the absence of EI-AEDs than in the presence of EI-AEDs (somnolence: 27.4% vs 16.7%; influenza: 11.0% vs 8.3%; irritability: 12.3% vs 2.8%; aggression: 11.0% vs 2.8%; bronchitis 6.8% vs 2.8%, respectively).
8.3 Less Common Clinical Trial Adverse Reactions
The following are treatment-emergent adverse reactions reported in at least 3 patients treated with FYCOMPA in pooled Phase 3 studies (partial-onset and primary generalized tonic-clonic), that are also; numerically greater than placebo, and not described in other tables and sections.
Blood and Lymphatic System Disorders: anaemia, leukopenia, neutropenia, thrombocytopenia
Cardiac Disorders: Tachycardia
Ear and Labyrinth Disorders: ear pain, motion sickness, tinnitus
Eye Disorders: lacrimation increased
Gastrointestinal Disorders: abdominal discomfort, constipation, gastric disorder, gastritis, gastroesophageal reflux disease, gingivitis, toothache
General Disorders and Administration Site Conditions: asthenia, chest discomfort, feeling drunk, malaise, pyrexia
Hepatobiliary Disorders: cholelithiasis
Infections and Infestations: acute sinusitis, bronchitis, candidiasis, lower respiratory tract infection, pharyngitis, pharyngitis streptococcal, respiratory tract infection, tonsillitis
Injury, Poisoning and Procedural Complications: accidental overdose, chest injury, drug toxicity, facial bones fracture, foot fracture, hand fracture, joint injury, laceration, limb injury, lip injury, road traffic accident, wrist fracture
Investigations: aspartate aminotransferase increased, blood creatinine phosphokinase increased, blood sodium decreased, blood triglycerides increased, electrocardiogram QT prolonged, haemoglobin decreased
Metabolism and Nutrition Disorders: appetite disorder, decreased appetite, hypercholesterolaemia, increased appetite
Musculoskeletal and Connective Tissue Disorders: arthritis, muscle spasms
Nervous System Disorders: drooling, amnesia, post-traumatic headache, simple partial seizure, speech disorder, syncope, tremor
Psychiatric Disorders: abnormal behaviour, affect lability, disorientation, nervousness, mood swings, panic attack, sleep disorder, stress
Renal and Urinary Disorders: pollakiuria
Reproductive System and Breast Disorders: menorrhagia
Skin and Subcutaneous Tissue Disorders: acne, hypoaesthesia facial, pruritus, rash papular
Vascular Disorders: hypotension
8.5 Post-Market Adverse Reactions
The following adverse events not seen in controlled clinical studies have been observed in named patient programs or post-marketing experience. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure:
Hypersensitivity: Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)
Psychiatric: Acute psychosis, hallucinations, delusions, paranoia, delirium, confusional state, disorientation, memory impairment
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
The most significant known interactions with FYCOMPA are with:
- Moderate and strong CYP3A4/5 inducer anti-epileptic drugs (AEDs) carbamazepine, phenytoin and oxcarbazepine;
- Alcohol;
- Oral contraceptives containing levonorgestrel
9.3 Drug-Behavioural Interactions
Patients should be advised about the potential for somnolence or dizziness and advised not to drive or operate heavy machinery until they have gained sufficient experience on FYCOMPA to gauge whether it adversely affects their mental and/or motor performance.
9.4 Drug-Drug Interactions
Interactions between FYCOMPA and other anti-epileptic drugs (AEDs): Potential interactions between FYCOMPA (up to 12 mg once daily) and other AEDs were assessed in clinical studies examining partial-onset or primary generalized tonic-clonic seizures, and evaluated in a population PK analysis of pooled data from 20 studies in healthy subjects, two Phase 2 and six Phase 3 studies.
The consequences of these interactions on average steady state concentrations are summarized in Table 8 below.
Concomitant CYP3A-inducing AEDs: substantial decrease in FYCOMPA concentrations: The concomitant use of known moderate or strong CYP3A4/5 enzyme inducers (carbamazepine, phenytoin, oxcarbazepine) have been shown to substantially increase FYCOMPA clearance and consequently to decrease plasma concentrations of FYCOMPA by 45-65%. Starting dose and frequency of titration increase are altered accordingly in the presence of these three AEDs, but there are a lack of data to support dose corrections at the high end of dosing. This effect should also be taken into account and managed when adding or withdrawing these anti-epileptic drugs from a patient’s treatment regimen. (See also 7 WARNINGS AND PRECAUTIONS, General).
Table 8: FYCOMPA Interactions with AEDs
AED coadministered | Influence of AED on FYCOMPA concentration | Influence of FYCOMPA on AED concentration |
|---|---|---|
| Carbamazepine | ~65% decrease | <10% decrease |
| Oxcarbazepine | ~50% decrease | 35% increase 1 |
| Phenytoin | 50% decrease | No influence |
| Clobazam | No influence | <10% decrease |
| Clonazepam | No influence | No influence |
| Lamotrigine | No influence | <10% decrease |
| Levetiracetam | No influence | No influence |
| Phenobarbital | ~20% decrease | No influence |
| Topiramate | 20% decrease | No influence |
| Valproic Acid | No influence | <10% decrease |
| Zonisamide | No influence | No influence |
- 1) Active metabolite monohydroxycarbazepine was not assessed.
Oxcarbazepine is rapidly metabolised by cytosolic reductase enzyme to the active metabolite, monohydroxycarbazepine; the effect of perampanel on monohydroxycarbazepine concentrations is not known.
Concomitant AEDs with induction effects other than CYP3A4/5: potential for interaction with FYCOMPA: The potential for adverse drug interaction with FYCOMPA cannot be excluded for other CYP450 strong inducers. In a population pharmacokinetic analysis of patients with partial-onset seizures and primary generalized tonic-clonic seizures, in clinical studies (40 patients co-administered phenobarbital and 9 patients co-administered primidone) no effect on perampanel AUC was found; however, a modest effect of phenobarbital and primidone to decrease perampanel concentrations cannot be excluded.
Effect of other strong cytochrome P450 inducers on FYCOMPA (including rifampicin, St John’s Wort): Strong inducers of cytochrome P450, such as rifampicin, hypericum (St. John’s Wort) and some anti-retrovirals, are expected to decrease FYCOMPA concentrations (See also 7 WARNINGS AND PRECAUTIONS, General).
Effect of strong cytochrome P450 inhibitors on FYCOMPA (including ketoconazole and clarithromycin): Strong inhibitors of CYP450, such as ketoconazole and clarithromycin, are expected to increase FYCOMPA concentrations. Co-administration of single 1-mg dose of FYCOMPA with 400 mg once-daily doses of ketoconazole, a strong CYP3A4 inhibitor, for 8 days in healthy subjects increased FYCOMPA AUC by 20% and prolonged FYCOMPA half-life by 15% (68h vs 58h). However, larger effects cannot be excluded with clinically effective doses of FYCOMPA (4- 12 mg), nor with ketoconazole given for longer treatment duration. As well, larger effects may be seen when FYCOMPA is combined with a CYP3A inhibitor with longer half-life than ketoconazole.
Effect of FYCOMPA on CYP3A substrates such as Midazolam: In healthy subjects, FYCOMPA (6 mg once daily for 20 days) decreased midazolam (4 mg single-dose) AUC by 13%. A larger decrease in exposure of midazolam (or other sensitive CYP3A substrates) at higher FYCOMPA doses cannot be excluded.
Oral contraceptives: In healthy women receiving 12 mg (but not 4 or 8 mg/day) for 21 days concomitantly with a combined oral contraceptive (single dose of 30 μg ethinylestradiol and 150 μg levonorgestrel), FYCOMPA was shown to decrease the levonorgestrel exposure by approximately 40% (mean Cmax and AUC values). Ethinylestradiol AUC was not affected by FYCOMPA 12 mg whereas Cmax was decreased by 18%. Therefore, use of FYCOMPA with oral or implant contraceptives containing levonorgestrel may render them less effective and an additional reliable non-hormonal method (intra-uterine device (IUD), condom) is to be used (see 7.1.1 Pregnant Women, Women of Childbearing Potential and Hormonal Contraceptives).
Alcohol and other CNS depressants: The effects of FYCOMPA on tasks involving alertness and vigilance such as driving ability were additive or supra-additive to the effects of alcohol itself, as found in a pharmacodynamic interaction study in healthy subjects. Multiple dosing of FYCOMPA 12 mg/day increased levels of anger, confusion, and depression as assessed using the Profile of Mood State 5-point rating scale (see 10.2 Pharmacodynamics, Interactions with Alcohol). Therefore, patients taking FYCOMPA should be advised to avoid the use of alcohol (see 7 WARNINGS AND PRECAUTIONS, Psychiatric). These effects may also be seen when FYCOMPA is used in combination with other central nervous system (CNS) depressants (e.g., benzodiazepines, narcotics, barbiturates, sedating antihistamines).
Levodopa: In healthy subjects, FYCOMPA (4 mg once daily for 19 days) had no effect on Cmax or AUC of levodopa (100 mg single dose).
Pediatrics: Drug-drug interaction studies have only been performed in adults. In a population pharmacokinetic analysis of adolescent patients aged ≥12 years and children aged 7 to <12 years, there were no significant differences in any of the parameters compared to the adult population.
9.5 Drug-Food Interactions
Perampanel is almost completely absorbed after oral administration. When FYCOMPA was administered with a high-fat meal, the extent of absorption did not change significantly; however, the peak plasma concentration (Cmax) was 11-22% lower and tmax was delayed 1-2 hours compared to that under fasted conditions (see 10.3 Pharmacokinetics, Absorption).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Perampanel appears to be a selective, non-competitive antagonist of the ionotropic α-amino-3-hydroxy-5-methyl-4-isoxazolepropionic acid (AMPA) glutamate receptor on post-synaptic neurons. The precise mechanism by which perampanel exerts its antiepileptic effects in humans remains to be fully elucidated.
10.2 Pharmacodynamics
Pharmacokinetic-pharmacodynamic (efficacy) analyses were performed based on the data from clinical trials for each of: Partial-onset seizures (pooled from 3 studies; n = 1109 patients), and primary generalized tonic-clonic (1 study; n = 149 patients). In both cases, perampanel exposure is correlated with reduction in seizure frequency.
Psychomotor Performance: In a healthy volunteer study to assess the effects of perampanel on psychomotor performance using a standard battery of assessments including simulated driving, single and multiple doses of 8 mg and 12 mg impaired psychomotor performance in a dose-related manner. Performance testing returned to baseline within 2 weeks of cessation of perampanel dosing.
Alertness and Mood: Levels of alertness decreased in a dose-related manner in healthy subjects dosed with perampanel from 4 to 12 mg/day. Mood deteriorated following dosing of 12 mg/day only; the changes in mood were small and reflected a general lowering of alertness.
Interactions with Alcohol (psychomotor, alertness and mood): In the above study (see Psychomotor Performance), when administered to healthy subjects receiving alcohol to achieve a blood concentration of 80-100 mg/100mL, perampanel consistently impaired simple psychomotor performance after single doses of 4 to 12 mg, and after 21 days of multiple 12 mg/day doses. The effects of perampanel on complex tasks such as driving ability were additive or supra-additive to the impairment effects of alcohol. In another study (see Alertness and Mood, above), perampanel magnified the negative effects of alcohol on vigilance and alertness, and on anger, confusion, and depression.
Cardiac Electrophysiology: Electrocardiographic effects of perampanel were determined in a double-blind, randomized, placebo- and moxifloxacin-controlled clinical pharmacology study in healthy subjects. Perampanel was administered in daily doses of up to 12 mg/day for 7 days. There was no evidence that perampanel caused QT interval prolongation of clinical significance at doses of 6 or 12 mg (i.e., the upper bound of the 95% confidence interval for the largest placebo-adjusted baseline-corrected QTc was below 10 msec). There was no evidence that perampanel had a dose-related or clinically important effect on QRS duration.
10.3 Pharmacokinetics
Pharmacokinetics of perampanel are similar in healthy subjects, and patients with seizures (partial onset or PGTC). The half-life of perampanel is about 105 hours in adults, so that steady state is reached in about 2-3 weeks.
In healthy adult subjects, plasma concentrations of perampanel increased in direct proportion to administered doses over the range of 2 to 12 mg. In a population pharmacokinetic analysis of patients with seizures (partial onset or PGTC) receiving perampanel up to 8 or 12 mg/day, respectively, in placebo-controlled clinical studies, a linear relationship was found between dose and perampanel plasma concentrations.
Absorption:
Perampanel is readily absorbed after oral administration with no evidence of marked first-pass metabolism (absolute bioavailability is approximately 100%). Median time to reach peak concentration (tmax) ranged from 0.5 to 2.5 hours under fasted conditions. Co-administration of perampanel tablet with a high fat meal had no significant impact on the total exposure (AUC0-72h) to perampanel. The peak plasma exposure (Cmax) was reduced by 11-22% and tmax was delayed by approximately 1-2 hours compared to that under fasted conditions.
Distribution:
Data from in vitro studies indicate that, in the concentration range of 20 to 2000 ng/mL, perampanel is approximately 95% bound to plasma proteins, mainly albumin and α 1-acid glycoprotein. Blood to plasma ratio of perampanel is 0.88.
Results from in vitro studies indicate that perampanel is not a substrate or significant inhibitor of organic anion transporting polypeptides (OATP) 1B1 and 1B3, organic anion transporters (OAT) 1, 2, 3, and 4, organic cation transporters (OCT) 1, 2, and 3, and the efflux transporters P-glycoprotein and Breast Cancer Resistance Protein (BCRP).
Metabolism:
Perampanel is extensively metabolized via primary oxidation and sequential glucuronidation. The metabolism of perampanel is mediated primarily by CYP3A based on clinical study results in healthy subjects administered radiolabeled perampanel and supported by in vitro studies using recombinant human CYPs and human liver microsomes.
Following administration of radiolabeled perampanel, unchanged perampanel accounted for approximately 74% of total radioactivity in systemic circulation, with metabolite mH26b accounting for approximately 6%, and remaining metabolites at 2% or less.
Elimination:
Following administration of a radiolabeled perampanel dose to 8 healthy adult male subjects, recovered radioactivity in excreta was primarily composed of a mixture of oxidative and conjugated metabolites, with approximately 70% in feces, and 30% in urine. The components that made up the largest percentage (%) of recovered radioactivity in the excreta were: metabolites produced via CYP3A: M1 and M4, at 13% and 9% respectively; and parent drug at 6%.
In a population pharmacokinetic analysis of pooled data from 19 Phase 1 studies, the average t1/2 of perampanel was 105 hours. When dosed in combination with the strong CYP3A inducer carbamazepine, the average t1/2 was 25 hours. Apparent clearance of perampanel in healthy subjects and patients was approximately 12 mL/min.
Special Populations and Conditions
- Pediatrics
Pediatrics (< 7 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of FYCOMPA in pediatric patients below 7 years of age have not been established; therefore, Health Canada has not authorized an indication for this patient population. Data from population pharmacokinetic (modelling) studies in patients 4 to 6 years of age show exposure in this population was about 75% higher compared to adults receiving similar doses.
Pediatrics (7 to 11 years of age): Two open-label studies 232 and 311 were conducted to evaluate pharmacokinetics, safety and tolerability of FYCOMPA as adjunctive therapy in 135 pediatric patients 7 to 11 years of age, with various types of seizures, for which pharmacokinetic data were available, and of whom a minimum of 111 patients were with partial-onset seizures. Pharmacokinetic data from
Studies 311 and 232 were analyzed in a population pharmacokinetic study to support the extrapolation approach which aimed at achieving similar systemic exposure (plasma concentrations) of FYCOMPA in this patient population compared to adults receiving the recommended doses (see 7.1.3 Pediatrics and 8.2.1 Clinical Trial Adverse Reactions – Pediatrics).
Adolescents (12 to 17 years of age): A total of 258 patients aged 12 to 17 years received FYCOMPA tablets in controlled trials of partial-onset seizures or PGTC seizures. In a pooled population pharmacokinetic analysis of these adolescent (152) patients, apparent clearance of perampanel in adolescents was similar to adults (617).
- Geriatrics (≥ 65 years of age): In a population pharmacokinetic analysis of n = 11 patients ≥ 65 years of age with partial-onset seizures receiving FYCOMPA tablets up to 12 mg/day in placebo-controlled studies, no significant effect of age on perampanel apparent clearance was found.
- Sex: In a population pharmacokinetic analysis of patients with partial-onset or PGTC seizures, receiving FYCOMPA tablets up to 12 or 8 mg/day in placebo-controlled clinical studies, perampanel clearance was 18% lower in females compared to males. No dose adjustment is necessary based on gender.
- Ethnic Origin: In a population pharmacokinetic analysis of patients with partial-onset or PGTC seizures, receiving FYCOMPA tablets up to 12 or 8 mg/day in placebo-controlled studies, and including 614 Caucasians, 108 non-Chinese Asians, 97 Chinese, and 15 Blacks, there was no evidence of a significant effect of race on FYCOMPA clearance.
- Hepatic Insufficiency: The pharmacokinetics of FYCOMPA following a single 1 mg tablet dose were evaluated in 12 subjects with mild and moderate hepatic impairment (Child-Pugh A and B, respectively) compared with 12 healthy, demographically matched subjects. The total (free and protein bound) exposure (AUC0-inf) of FYCOMPA was 50% greater in subjects with mild hepatic impairment and more than doubled (2.55-fold) in subjects with moderate hepatic impairment compared to their healthy controls. The AUC0-inf of free FYCOMPA in subjects with mild and moderate hepatic impairment was 1.8-fold and 3.3-fold, respectively, of those in matched healthy controls. The t1/2 was prolonged in mildly impaired (306 h vs 125 h), and moderately impaired (295 h vs 139 h) subjects compared to matched healthy subjects. FYCOMPA has not been studied in subjects with severe hepatic impairment.
Renal Insufficiency: A dedicated study has not been conducted to evaluate the pharmacokinetics of FYCOMPA in patients with renal impairment. Population pharmacokinetic analysis was performed on pooled data from patients with partial-onset seizures or PGTC seizures receiving FYCOMPA tablets up to 12 or 8 mg/day, respectively, in placebo-controlled clinical studies. Mild renal impairment was defined as creatinine clearance <80 mL/min (n = 59 of 764 total). Results showed that, in the presence of concomitant CYP3A-inducing AEDs, apparent clearance was slightly lower by 15.5% in patients with mild renal impairment (n= 30) compared to patients with
- normal renal function (n= 442), with a corresponding 18 % higher AUC. In contrast, in the absence of concomitant CYP3A-inducing AEDs, FYCOMPA apparent clearance was slightly higher by 10.5% in patients with mild renal impairment (n=49) compared to patients with normal renal function (n=332), with a corresponding 10% lower AUC. Considering the substantial overlap in the exposure between normal and mildly impaired patients, no dosage adjustment is necessary for patients with mild renal impairment. There were insufficient patients with moderate renal impairment to support dosing in this population. FYCOMPA has not been studied in patients with severe renal impairment and patients undergoing hemodialysis.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature (15°C - 30°C). Keep out of the reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: perampanel
Chemical name: 2-(2-oxo-1-phenyl-5-pyridin-2-yl-1,2-dihydropyridin-3-yl) benzonitrile hydrate (4:3)
Molecular formula and molecular mass: C23H15N3O • ¾ H2
362.90 (3/4 hydrate)
Structural formula:
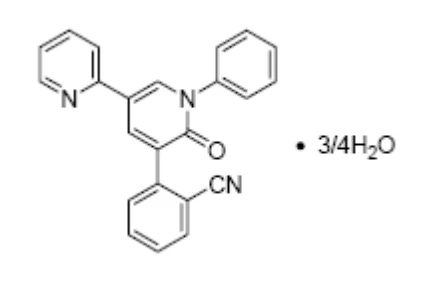
Physicochemical properties: Perampanel is a white to yellowish white powder. It is freely soluble in N-methylpyrrolidone, sparingly soluble in acetonitrile and acetone, slightly soluble in methanol, ethanol and ethyl acetate, very slightly soluble in 1-octanol and diethyl ether and practically insoluble in heptane and water.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication, Trial Design and Study Demographics
Partial-Onset Seizures:
- Studies 304, 305 and 306:
Study Demographics and Trial Designs: The efficacy of FYCOMPA in partial-onset seizures, with or without secondary generalization, was studied in patients who were not adequately controlled with 1 to 3 concomitant AEDs in 3 randomized, double-blind, placebo-controlled, multicenter studies (Studies 304, 305 and 306). A total of 939 adult patients and 98 adolescents (12-17 years of age) were treated with FYCOMPA doses 2-12 mg/day. All studies had an initial 6-week Baseline Period, during which patients were required to have more than five seizures in order to be randomized. The Baseline Period was followed by a 19 week Treatment Period, consisting of a 6 week Titration Phase and a 13 week Maintenance Phase.
Patients in these 3 studies had a mean duration of epilepsy of approximately 21 years and a median baseline seizure frequency ranging from 9.3 to 14.3 seizures per 28 days. During the studies, more than 85% of patients were taking 2 to 3 concomitant AEDs with or without concurrent vagal nerve stimulation, and approximately 50% were on at least one AED known to induce CYP3A, an enzyme family critical to the metabolism of FYCOMPA (i.e. carbamazepine, oxcarbazepine, or phenytoin), resulting in a significant reduction in FYCOMPA’s serum concentration (see 9.4 Drug-Drug Interactions, Interactions between FYCOMPA and other anti-epileptic drugs (AEDs)). Concomitant AEDs taken by at least 10% of the patients in the total placebo and perampanel group were: carbamazepine (34%), lamotrigine (32%), valproic acid (31%), levetiracetam (30%), topiramate (20%), oxcarbazepine (18%) and clobazam (11%).
Each study evaluated placebo and multiple FYCOMPA dosages (see Table 9). During the Titration Period in all 3 studies, patients on FYCOMPA received an initial 2 mg once daily dose, which was subsequently increased by 2 mg at weekly increments to reach the final target dose. Patients experiencing intolerable adverse reactions with dose increases were permitted to remain in the study at a reduced dose.
The primary endpoint in Studies 304, 305, and 306 was the percent change in partial-onset seizure frequency per 28 days during the Treatment Period as compared to the Baseline Period.
Study Results: A statistically significant decrease in seizure rate was observed at doses of 4 to 12 mg per day (see Table 9). Dose response was apparent at 4 to 8 mg with little additional reduction in seizure frequency at 12 mg per day. Results of the 50% Responder Rates also support the results of the primary efficacy endpoint.
Table 9: Summary: Median Percent Reduction in 28-day Total Partial Seizure Frequency from Baseline over the double-blind Treatment Phase (primary efficacy end-point) and of Responder Rates in the Maintenance Phase (secondary endpoint). In these studies, a total of 939 adults and 98 adolescents were treated with FYCOMPA.
Study n=population in double-blind phase | AEDs + Placebo | AEDs + FYCOMPA | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 2mg/day | 4 mg/day | 8 mg/day | 12 mg/day | ||||||||||||||
| Study 304 | |||||||||||||||||
| Median Baseline Seizure Frequency | 13.7 | - | - | 14.3 | 12.0 | ||||||||||||
| N | 121 | - | - | 133 | 133 | ||||||||||||
| Median % Reduction | 21% | - | - | 26%* | 35%* | ||||||||||||
| 50% Responder rate1 | 26% | - | - | 38% | 36% | ||||||||||||
| Study 305 | |||||||||||||||||
| Median Baseline Seizure Frequency | 11.8 | - | - | 13.0 | 13.7 | ||||||||||||
| N | 136 | - | - | 129 | 121 | ||||||||||||
| Median % Reduction | 10% | - | - | 31%*** | 18%* | ||||||||||||
| 50% Responder rate1 | 15% | - | - | 33%** | 34%*** | ||||||||||||
| Study 306 | |||||||||||||||||
| Median Baseline Seizure Frequency | 9.3 | 10.1 | 10.0 | 10.9 | - | ||||||||||||
| N | 184 | 180 | 172 | 169 | - | ||||||||||||
| Median % Reduction | 11% | 14% | 23%** | 31%*** | - | ||||||||||||
| 50% Responder rate1 | 18% | 21% | 29%* | 35%*** | - | ||||||||||||
| Combined Studies (Study 304, 305 and 306) | |||||||||||||||||
| Median Baseline Seizure Frequency | 11.1 | 10.1 | 10.0 | 12.2 | 13.0 | ||||||||||||
| N | 441 | 180 | 172 | 431 | 254 | ||||||||||||
| Median % Reduction | 13% | 14% | 23% | 29% | 27% | ||||||||||||
| 50% Responder rate1 | 19% | 21% | 29% | 35% | 35% | ||||||||||||
-Dose not studied *, **, *** for p<0.05, p<0.01 and p < 0.001 (p-value not shown for combined studies) 150% Responder rate = percentage of patients with ≥50% reduction in 28-day total seizure frequency from Baseline to the Maintenance Phase | |||||||||||||||||
Table 10 presents an analysis combining data from all 3 studies, grouping patients based upon whether or not concomitant CYP3A enzyme-inducers AEDs (EI-AEDs) were used. The analysis revealed a reduced treatment effect in the presence of concomitant EI-AEDS.
Table 10: Median Treatment Effect for Combined Studies (Study 304, 305 and 306) Based on the Presence or Absence of Concomitant CYP3A-Inducing AEDs (carbamazepine, oxcarbazepine, phenytoin)*
There were no significant differences in seizure control as a function of gender.
- Study 335:
This regional, Asia-Pacific trial was a multicenter, randomized, double-blind, placebo-controlled, parallel group study to assess the efficacy of FYCOMPA (4, 8, and 12 mg) compared to placebo given as an adjunctive therapy in patients with POS. Patients were randomized to 1 of 4 treatment groups (4, 8, 12 mg/day, or placebo) in a 1:1:1:1 ratio. A total of 62 male and female adolescent patients (12 to 17 years), as well as 467 adult patients (≥18 years of age) who had a diagnosis of POS, were treated with FYCOMPA. Majority of the patients were Asian (94%), followed by Caucasian (5%). Approximately 53% of the patients were receiving a CYP3A inducer. Approximately 84% of the FYCOMPA-treated patients completed the study (Placebo: 86%).
The primary efficacy endpoint in this study was the percent change in POS frequency per 28 days during the Treatment Period relative to the Baseline Period. Responder Rate (Percentage of patients
| Median Percent Reduction | Responder Rate** | |||
|---|---|---|---|---|
| Without Inducers | With Inducers | Without Inducers | With Inducers | |
Placebo n=441 | 13% | 8% | 17% | 18% |
2 mg/day n=180 | 18% | 8% | 23% | 19% |
4 mg/day n=172 | 21% | 25% | 34% | 24% |
8 mg/day n=431 | 44% | 23% | 47% | 28% |
12 mg/day n=254 | 39% | 18% | 47% | 30% |
* Patients from Latin America region excluded because of significant treatment-by-region interaction due to high placebo response. **The proportion of patients with at least a 50% decrease in seizure frequency. | ||||
with ≥50% reduction in 28-day total seizure frequency from Baseline to the Maintenance Phase) was a key secondary efficacy end-point.
Study 335 Results: A statistically significant decrease was observed in POS frequency per 28 days during the Treatment Period relative to the Baseline Period. The responder rate was numerically greater for FYCOMPA than for the respective placebo group
- Study 311:
The efficacy of FYCOMPA as adjunctive therapy in the treatment of partial onset seizures in patients 7 to 11 years of age was established based on extrapolation of efficacy in a Population Pharmacokinetic study (see 10.3 Pharmacokinetics).
Primary Generalized Tonic-Clonic (PGTC) Seizures:
- Study 332:
Study Demographics and Trial Designs: The efficacy of FYCOMPA as adjunctive therapy in patients experiencing primary generalized tonic-clonic seizures (PGTCs) was assessed in one multicenter, randomized, double-blind, placebo-controlled study (Study 332). Eligible patients on a stable dose of 1 to 3 AEDs experiencing at least 3 PGTCs during the 8-week Baseline Period were randomized to either FYCOMPA (n=81; 68 adult patients and 13 adolescents) or placebo (n=81; 72 adult patients and 9 adolescents).
The Baseline Period was followed by a 17 week Treatment Period, consisting of a 4 week Titration Phase and 13 week Maintenance Phase.
Patients had a mean duration of epilepsy of approximately 17 years. Approximately 30% of the patients experienced only PGTC seizures; the remaining patients experienced one or more seizures types in addition to tonic-clonic. Absence seizures were reported by 50% of the patients, and myoclonic seizures by 40%. With respect to the number of concomitant AEDS taken at baseline, the frequency distribution was similar for the two treatment groups: approximately 30% were taking only 1 AED; 50% were taking 2; and 20% were taking 3 AEDs. For a total of 27 patients, these included an EI-AED (11% in the perampanel group, 22.0% in the placebo group).
Patients were titrated over 4 weeks up to a maximum dose of 8 mg per day or the highest tolerated dose.
The primary efficacy endpoint was the percent change in primary generalized tonic-clonic seizure frequency per 28 days during the Treatment Period as compared to the Baseline Period. Responder rate (Proportion of patients with ≥50% decrease in seizure frequency) was a key secondary efficacy end-point.
Study 332 results: A statistically significant decrease in seizure rate was observed with FYCOMPA compared to placebo (Table 11). Results of the 50% Responder Rates also support the results of the primary efficacy endpoint.
Table 11: Median Percent Reduction in 28-day Total PGTC Seizure Frequency from Baseline over the double-blind Treatment Phase (primary efficacy end-point), with Responder Rates in the Maintenance Phase (secondary endpoint) in Study 332. In this study, a total of 68 adults and 13 adolescents were treated with FYCOMPA.
AEDs + Placebo (N=81) | AEDs + FYCOMPA (N=81) | ||||
| Median Baseline Seizure Frequency | 2.5 | 2.6 | |||
| Median % Reduction | 38% | 76%a | |||
| 50% Responder Rateb | 40% | 64% | |||
| a P-value compared to placebo: <0.0001 | |||||
bThe proportion of patients with at least a 50% decrease in seizure frequency.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Repeated Dose Toxicity: Maximum tolerated dose (MTD) administration to rats (100 mg/kg/day in males and 30 mg/kg/day in females) for 13 or 26 weeks and in cynomolgus monkeys (8 mg/kg/day in both sexes) for 39 weeks resulted in severe pharmacologically-based CNS clinical signs and decreased terminal body weight. There were no changes directly attributable to perampanel in clinical pathology or histopathology. The systemic exposures (Cmax and AUC) at MTD were approximately equivalent or lower than the exposures in human at the maximum recommended human dose (MRHD) of 12 mg per day.
In oral repeated-dose toxicity studies of 4 to 52 weeks, the primary finding in all species was effects on CNS, including abnormal gait, reduced motor activity and/or prostration were observed in all species. In studies of up to 13 weeks in mice, these CNS clinical signs were accompanied by decreases in body weight gains and food consumption. In oral repeated dose toxicity studies for up to 26 weeks in rats, CNS clinical signs and decreases in body weight gain and food consumption were observed at 30 mg/kg and 60 mg/kg. In studies of up to 13 weeks in dogs, CNS clinical signs were observed at 1 mg/kg and higher. In studies in cynomolgus monkeys for up to 52 weeks, clinical signs such as ataxic gait; decreased activity, sitting position, and transient prostration were observed. Death due to severe adverse clinical signs occurred at the highest dose tested (8 mg/kg) in the 39−week study. The observed CNS clinical signs of abnormal gait, reduced motor activity and/or prostration are not unexpected findings for an AMPA antagonist. These dosage-related clinical signs were mainly related to Cmax and were observed in general when Cmax approached approximately 1400 ng/mL (10 – 30 mg/kg) in mice, 500 ng/mL (10 – 30 mg/kg) in rats, 80 ng/mL (1 mg/kg) in dogs, and 300 ng/mL (1 mg/kg) in monkeys. There was no organ toxicity or histopathologic findings at any dose in any of the species.
Clinical signs consistent with excessive grooming/scratching and/or self-mutilation were observed in the adult mouse, rat and rabbit, and in the juvenile rat and dog. It remains unclear whether the apparent self-mutilation is an extension of the excessive grooming or a separate behavioural effect. It is primarily in the juvenile animals that the actual behaviour of excessive grooming was observed; otherwise, it was generally inferred from the injuries. Mortality due to skin lesions attributed to excessive grooming was observed at 60 mg/kg and higher in repeated-dose toxicity studies in mice. Deaths or morbidity occurred in rats after severe clinical signs including excessive grooming and self-mutilation in males given 100 mg/kg and higher and in females given 30 mg/kg and higher. In the carcinogenicity study in the mouse, similar clinical signs including loss of fore-hind limbs and loss of digits were observed at doses of > 3mg/kg/day. “Increase in grooming” was observed in adult rats and rabbits in reproductive studies, accompanied by “swelling of limbs” in the rat. “Excessive scratching” was observed at all doses in studies of the juvenile rat and dog. “Excessive grooming” was observed in a 13-week phototoxicity study in hairless mice. Thus, excessive scratching/grooming was observed (or inferred from excoriations and other grooming-related injuries) in adult rats and mice, as well as in juvenile rats and dogs. The clinical relevance of these data to humans is unknown.
Carcinogenicity: Perampanel was administered orally to mice (1, 3, 10, or 30 mg/kg/day) and rats (10, 30, or 100 mg/kg/day in males; 3, 10, or 30 mg/kg/day in females) for up to 104 weeks. There was no evidence of drug-related tumors in either species. Plasma perampanel exposures (AUC) at the highest doses tested were less than that in humans dosed at 8 mg/day.
Perampanel was negative in the in vitro Ames and mouse lymphoma assays, and in the in vivo rat micronucleus assay.
Reproductive and Developmental Toxicology: In male and female rats administered perampanel (oral doses of 1, 10, or 30 mg/kg/day) prior to and throughout mating and continuing in females to gestation day 6, there were no clear effects on fertility. Prolonged and/or irregular estrus cycles were observed at all doses but particularly at the highest dose tested. Plasma perampanel exposures (AUC) at all doses were lower than that in humans dosed at 8 mg/day.
In animal studies, perampanel induced developmental toxicity in pregnant rat and rabbit at clinically relevant doses. Oral administration of perampanel (1, 3, or 10 mg/kg/day) to pregnant rats throughout organogenesis resulted in an increase in visceral abnormalities (diverticulum of the intestine) at all doses tested. In a dose-ranging study at higher oral doses (10, 30, or 60 mg/kg/day), embryo lethality and reduced fetal body weight were observed at the mid and high doses tested. The lowest dose tested (1 mg/kg/day) is similar to a human dose of 8 mg/day based on body surface area (mg/m2).
Upon oral administration of perampanel (1, 3, or 10 mg/kg/day) to pregnant rabbits throughout organogenesis, embryo lethality was observed at the mid and high doses tested; the no effect dose for embryo-fetal developmental toxicity in rabbit (1 mg/kg/day) is approximately 2 times a human dose of 8 mg/day based on body surface area (mg/m2).
Oral administration of perampanel (1, 3, or 10 mg/kg/day) to rats throughout gestation and lactation resulted in fetal and pup deaths at the mid and high doses and delayed sexual maturation in males and females at the highest dose tested. No effects were observed on measures of neurobehavioural or reproductive function in the offspring. The no-effect dose for pre- and postnatal developmental toxicity in rat (1 mg/kg/day) is similar to a human dose of 8 mg/day based on body surface area (mg/m2).