


Product Monograph - Idacio (Fresenius Kabi Canada, PM 00083255)
RECENT MAJOR LABEL CHANGES
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 5
1 INDICATIONS ................................................................................................................ 5
1.1 Pediatrics ................................................................................................................. 6
1.2 Geriatrics ................................................................................................................. 7
2 CONTRAINDICATIONS .................................................................................................. 7
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................. 7
4 DOSAGE AND ADMINISTRATION .................................................................................. 9
4.1 Dosing Considerations ............................................................................................. 9
4.2 Recommended Dose and Dosage Adjustment ....................................................... 10
4.4 Administration ....................................................................................................... 13
4.5 Missed Dose ........................................................................................................... 14
| 1 INDICATIONS, Polyarticular Juvenile Idiopathic Arthritis | 2026-01 |
|---|---|
| 1 INDICATIONS, Crohn’s Disease | 2026-01 |
| 1 INDICATIONS, Pediatric Uveitis | 2026-01 |
| 1 INDICATIONS, 1.1 Pediatrics | 2026-01 |
| 4 DOSAGE AND ADMINISTRATION, 4.1 Dosing Consideration, Pediatrics | 2026-01 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment | 2026-01 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Polyarticular Juvenile Idiopathic Arthritis | 2026-01 |
| 4 DOSAGE AND ADMINISTRATION, 4.2 Recommended Dose and Dosage Adjustment, Pediatric Uveitis | 2026-01 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | 2026-01 |
| 7 WARNINGS AND PRECAUTIONS, Malignancies | 2026-01 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.3 Pediatrics | 2026-01 |
5 OVERDOSAGE ............................................................................................................. 14
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 14
7 WARNINGS AND PRECAUTIONS ................................................................................. 15
7.1 Special Populations ................................................................................................ 21
7.1.1 Pregnant Women ................................................................................................... 21
7.1.2 Breast-feeding ....................................................................................................... 22
7.1.3 Pediatrics ............................................................................................................... 22
7.1.4 Geriatrics ............................................................................................................... 22
8 ADVERSE REACTIONS ................................................................................................. 23
8.1 Adverse Reaction Overview ................................................................................... 23
8.2 Clinical Trial Adverse Reactions.............................................................................. 30
8.2.1 Clinical Trial Adverse Reactions – Pediatrics .......................................................... 48
8.3 Less Common Clinical Trial Adverse Reactions....................................................... 56
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ................................... 57
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .................................................................................................. 57
8.5 Post-Market Adverse Reactions ............................................................................. 58
9 DRUG INTERACTIONS ................................................................................................. 59
9.1 Serious Drug Interactions ....................................................................................... 59
9.2 Drug Interactions Overview ................................................................................... 59
9.3 Drug-Behavioural Interactions ............................................................................... 59
9.4 Drug-Drug Interactions .......................................................................................... 59
9.5 Drug-Food Interactions .......................................................................................... 60
9.6 Drug-Herb Interactions .......................................................................................... 61
9.7 Drug-Laboratory Test Interactions ......................................................................... 61
10 CLINICAL PHARMACOLOGY ........................................................................................ 61
10.1 Mechanism of Action ............................................................................................. 61
10.2 Pharmacodynamics ................................................................................................ 61
10.3 Pharmacokinetics ................................................................................................... 62
11 STORAGE, STABILITY AND DISPOSAL .......................................................................... 65
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................ 65
PART II: SCIENTIFIC INFORMATION ........................................................................................ 66
13 PHARMACEUTICAL INFORMATION ............................................................................. 66
14 CLINICAL TRIALS ......................................................................................................... 67
14.5 Clinical Trials - Reference Biologic Drug ................................................................. 67
15 MICROBIOLOGY ........................................................................................................ 112
16 NON-CLINICAL TOXICOLOGY – REFERENCE BIOLOGIC DRUG ...................................... 113
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 117
PATIENT MEDICATION INFORMATION .................................................................................. 118
INSTRUCTIONS FOR USE: ...................................................................................................... 127
INSTRUCTIONS FOR USE: ...................................................................................................... 131
PART I: HEALTH PROFESSIONAL INFORMATION
Idacio® (adalimumab injection) is a biosimilar biologic drug (biosimilar) to Humira® (adalimumab injection). A biosimilar is a biologic drug that was granted authorization based on a demonstration of similarity to a version previously authorized in Canada, known as the reference biologic drug.
1 INDICATIONS
Idacio is indicated for:
Rheumatoid Arthritis
- reducing the signs and symptoms, inducing major clinical response and clinical remission, inhibiting the progression of structural damage and improving physical function in adult patients with moderately to severely active rheumatoid arthritis. Idacio can be used alone or in combination with methotrexate (MTX) or other disease-modifying anti-rheumatic drugs (DMARDs).
When used as first-line treatment in recently diagnosed patients who have not been previously treated with MTX, Idacio should be given in combination with MTX. Idacio can be given as monotherapy in case of intolerance to MTX or when treatment with MTX is contraindicated.
Polyarticular Juvenile Idiopathic Arthritis
- in combination with MTX, reducing signs and symptoms of moderately to severely active polyarticular juvenile idiopathic arthritis in patients, 2 years of age and older, weighing ≥ 30 kg, who have had an inadequate response to one or more DMARDs. Idacio can be used as monotherapy in case of intolerance to MTX or when continued treatment with MTX is not appropriate (see 14.5 Clinical Trials - Reference Biologic Drug, Pediatric, Polyarticular Juvenile Idiopathic Arthritis, Study Results). Adalimumab injection has not been studied in pediatric patients with polyarticular juvenile idiopathic arthritis aged less than 2 years.
Psoriatic Arthritis
- reducing the signs and symptoms of active arthritis and inhibiting the progression of structural damage and improving the physical function in adult psoriatic arthritis patients. Idacio can be used in combination with MTX in patients who do not respond adequately to MTX alone.
Ankylosing Spondylitis
- reducing signs and symptoms in adult patients with active ankylosing spondylitis who have had an inadequate response to conventional therapy.
Crohn’s Disease
reducing signs and symptoms and inducing and maintaining clinical remission in adult patients with moderately to severely active Crohn’s disease who have had an inadequate response to conventional therapy, including corticosteroids and/or immunosuppressants.
- Idacio is indicated for reducing signs and symptoms and inducing clinical remission in these patients if they have also lost response to or are intolerant to infliximab.
Ulcerative Colitis
- treatment of adult patients with moderately to severely active ulcerative colitis (UC) who have had an inadequate response to conventional therapy including corticosteroids and/or azathioprine or 6-mercaptopurine (6-MP) or who are intolerant to such therapies. The efficacy of adalimumab injection in patients who have lost response to or were intolerant to TNF blockers has not been established.
Hidradenitis Suppurativa
- treatment of active moderate to severe hidradenitis suppurativa in adult and adolescent patients (12 to 17 years of age weighing ≥30 kg) who have not responded to conventional therapy (including systemic antibiotics).
Plaque Psoriasis
- treatment of adult patients with chronic moderate to severe plaque psoriasis who are candidates for systemic therapy. For patients with chronic moderate plaque psoriasis, Idacio should be used after phototherapy has been shown to be ineffective or inappropriate.
Adult Uveitis
- treatment of non-infectious uveitis (intermediate, posterior and panuveitis) in adult patients with inadequate response to corticosteroids or as corticosteroid sparing treatment in corticosteroid-dependent patients.
Pediatric Uveitis
- treatment of chronic non-infectious anterior uveitis in pediatric patients from 2 years of age weighing ≥ 30 kg, who have had an inadequate response to or are intolerant to conventional therapy, or in whom conventional therapy is inappropriate.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of adalimumab in pediatric patients has been established. Therefore, Health Canada has authorized indications for pediatric use.
Polyarticular Juvenile Idiopathic Arthritis
Adalimumab injection has not been studied in pediatric patients with polyarticular JIA less than 2 years of age or in pediatric patients with a weight below 10 kg.
Idacio is available for pediatric polyarticular juvenile patients who require the full 40 mg dose based on body weight (See 4 DOSAGE AND ADMINISTRATION, Recommended Dosage and Dosage Adjustment, Pediatrics, Polyarticular Juvenile Idiopathic Arthritis).
The auto-injector and pre-filled syringe are not designed to deliver a portion of the full 40 mg dose and must not be used in pediatric patients who require < 40 mg dose.
Adolescent Hidradenitis Suppurativa
There are no clinical trials with adalimumab injection in adolescent patients with hidradenitis suppurativa (HS). The dosage of adalimumab injection in these patients has been determined based on pharmacokinetic/pharmacodynamic modeling and simulation (see 14.5 Clinical Trials - Reference Biologic Drug, Pediatric, Adolescent Hidradenitis Suppurativa).
Pediatric Uveitis
Adalimumab injection has not been studied in pediatric patients with uveitis <2 years of age. Very limited data are available for pediatric patients with uveitis between 2 and <3 years of age.
Idacio is available for pediatric uveitis patients who require the full 40 mg dose based on body weight (See 4 DOSAGE AND ADMINISTRATION, Recommended Dosage and Dosage Adjustment, Pediatrics, Pediatric Uveitis).
The auto-injector and pre-filled syringe are not designed to deliver a portion of the full 40 mg dose and must not be used in pediatric patients who require < 40 mg dose.
1.2 Geriatrics
Evidence from clinical studies and experience suggests that use of adalimumab injection in the geriatric population is not associated with differences in effectiveness. See 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
- Patients with known hypersensitivity to Idacio or to any of its components. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Patients with severe infections such as sepsis, tuberculosis and opportunistic infections. See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX, Infections.
- Patients with moderate to severe heart failure (NYHA class III/IV). See 7 WARNINGS AND PRECAUTIONS, Cardiovascular, Patients with Congestive Heart Failure.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
Hepatosplenic T-Cell Lymphoma
Very rare post-marketing reports of hepatosplenic T-cell lymphoma (HSTCL), a rare aggressive lymphoma that is often fatal, have been identified in patients treated with adalimumab injection. Most of the patients had prior infliximab therapy as well as concomitant azathioprine or 6-mercaptopurine use for Crohn’s disease. The potential risk with the combination of azathioprine or 6-mercaptopurine and adalimumab should be carefully considered. The causal association of HSTCL with adalimumab is not clear.
Infections
Serious infections due to bacterial, mycobacterial, invasive fungal (disseminated or extrapulmonary histoplasmosis, aspergillosis, coccidioidomycosis), viral, parasitic, or other opportunistic infections have been reported in patients receiving tumor necrosis factor (TNF)-blocking agents. Sepsis, rare cases of tuberculosis, candidiasis, listeriosis, legionellosis and pneumocystis have also been reported with the use of TNF-blocking agents, including adalimumab injection. Other serious infections seen in clinical trials include pneumonia, pyelonephritis, septic arthritis and septicemia. Hospitalization or fatal outcomes associated with infections have been reported. Many of the serious infections have occurred in patients on concomitant immunosuppressive therapy that, in addition to their underlying disease, could predispose them to infections.
Treatment with Idacio should not be initiated in patients with active infections, including chronic or localized infections, until infections are controlled. In patients who have been exposed to tuberculosis, and patients who have travelled in areas of high risk of tuberculosis or endemic mycoses, such as histoplasmosis, coccidioidomycosis, or blastomycosis, the risk and benefits of treatment with Idacio should be considered prior to initiating therapy. See 7 WARNINGS AND PRECAUTIONS, Infections, Other Opportunistic Infections.
As with other TNF-blockers, patients should be monitored closely for infections (including tuberculosis) before, during and after treatment with Idacio.
Patients who develop a new infection while undergoing treatment with Idacio should be monitored closely and undergo a complete diagnostic evaluation. Administration of Idacio should be discontinued if a patient develops a serious infection or sepsis, and appropriate antimicrobial or antifungal therapy should be initiated.
Physicians should exercise caution when considering the use of Idacio in patients with a history of recurrent infection or with underlying conditions which may predispose them to infections, or patients who have resided in regions where tuberculosis and histoplasmosis are endemic. See 7 WARNINGS AND PRECAUTIONS, Infections, Tuberculosis and 8.1 Adverse Drug Reaction Overview, Infections. The benefits and risks of treatment with Idacio should be carefully considered before initiating therapy.
Pediatric Malignancy
Lymphoma and other malignancies, some fatal, have been reported in children and adolescent patients treated with TNF-blockers, including adalimumab injection. See 7 WARNINGS AND PRECAUTIONS, Malignancies, Malignancies in Pediatric Patients and Young Adults.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
Pediatrics
Polyarticular Juvenile Idiopathic Arthritis
See 4.2 Recommended Dosage and Dosage Adjustment, Pediatrics, Polyarticular Juvenile Idiopathic Arthritis.
Safety and effectiveness in pediatric patients with polyarticular JIA less than 2 years of age or in patients with a weight below 10 kg have not been established.
Adolescent Hidradenitis Suppurativa
See 4.2 Recommended Dosage and Dosage Adjustment, Pediatrics, Adolescent Hidradenitis Suppurativa.
There are no clinical trials with adalimumab injection in adolescent patients with hidradenitis suppurativa (HS). The dosage of adalimumab injection in these patients has been determined based on pharmacokinetic/ pharmacodynamic modeling and simulation.
Pediatric Uveitis
See 4.2 Recommended Dosage and Dosage Adjustment, Pediatrics, Pediatric Uveitis.
Safety and effectiveness in pediatric patients with uveitis <2 years of age have not been established. Very limited data are available for pediatric patients with uveitis between 2 and <3 years of age.
Geriatrics
Evidence from clinical studies and experience suggests that use of adalimumab injection in the geriatric population is not associated with differences in effectiveness. No dose adjustment is needed for this population. A brief discussion can be found under 7 WARNINGS AND PRECAUTIONS, Special Populations, Geriatrics.
Gender
No gender-related pharmacokinetic differences were observed after correction for a patient’s body weight. Healthy volunteers and patients with rheumatoid arthritis displayed similar adalimumab injection pharmacokinetics.
Race
No differences in immunoglobulin clearance would be expected among races. From limited data in non-Caucasians, no important kinetic differences were observed for adalimumab injection. Dosage adjustment is not required.
Hepatic Insufficiency
No pharmacokinetic data are available in patients with hepatic impairment. No dose recommendation can be made.
Renal Insufficiency
No pharmacokinetic data are available in patients with renal impairment. No dose recommendation can be made.
Disease States
Healthy volunteers and patients with rheumatoid arthritis displayed similar adalimumab injection pharmacokinetics. See 10.3 Pharmacokinetics, Special Populations and Conditions, Disease States.
Concomitant Medications
Methotrexate, glucocorticoids, salicylates, nonsteroidal anti-inflammatory drugs (NSAIDs), analgesics or other DMARDs may be continued during treatment with Idacio. When treated with Idacio as monotherapy, some rheumatoid arthritis patients who experience a decrease in their response to Idacio 40 mg every other week may benefit from an increase in dose intensity to Idacio 40 mg every week.
4.2 Recommended Dose and Dosage Adjustment
Idacio is only available as 40 mg pre-filled syringe and 40 mg auto-injector pen. Thus, it is not possible to administer Idacio to patients who require less than a full 40 mg dose.
Pediatrics
Polyarticular Juvenile Idiopathic Arthritis
The recommended dose of Idacio for patients with polyarticular JIA from 2 years of age weighing ≥ 30 kg is shown in (Table 1). Idacio is administered every other week via subcutaneous injection in patients who require the full 40 mg dose. Idacio can be used in combination with methotrexate or as monotherapy in case of intolerance to methotrexate or when continued treatment with methotrexate is not appropriate.
Table 1 Idacio Dose for Pediatric Patients with Polyarticular JIA
| Patient Weight* | Dosing Regimen |
|---|---|
| ≥30 kg | 40 mg every other week |
| * There is no dosage form of Idacio that allows weight-based dosing for pediatric patients below 30 kg. | |
Available data suggest that clinical response is usually achieved within 12 weeks of treatment. Efficacy and safety in patients who do not respond by Week 16 have not been established.
There is no relevant use of adalimumab injection in children aged <2 years in this indication.
Adolescent Hidradenitis Suppurativa
The recommended Idacio dose regimen for adolescent patients with HS (12 to 17 years of age weighing ≥30 kg) is 80 mg at Week 0 followed by 40 mg every other week starting at Week 1 via subcutaneous injection.
In adolescent patients with inadequate response to Idacio 40 mg every other week, an increase in dosing frequency to 40 mg every week may be considered (see 14.5 Clinical Trials - Reference Biologic Drug, Pediatric, Adolescent Hidradenitis Suppurativa).
Antibiotics may be continued during treatment with Idacio if necessary.
Continued therapy beyond 12 weeks should be carefully reconsidered in a patient with no improvement within this time period.
Pediatric Uveitis
The recommended dose of Idacio in combination with methotrexate for pediatric patients with chronic non-infectious anterior uveitis 2 years of age and older weighing ≥30 kg is shown in (Table 2). Idacio is administered every other week via subcutaneous injection in patients who require the full 40 mg dose. In pediatric uveitis, there is no experience in the treatment with adalimumab injection without concomitant treatment with methotrexate.
Table 2 Idacio Dose for Pediatric Patients with Uveitis Patient Weight Dosing Regimen
| Patient Weight* | Weight Dosing Regimen |
|---|---|
| ≥30 kg | 40 mg every other week in combination with methotrexate |
* There is no dosage form of Idacio that allows weight-based dosing for pediatric patients below 30 kg.
When Idacio is initiated in patients ≥6 years of age, an optional loading dose of 80 mg for patients ≥30 kg may be administered one week prior to the start of maintenance therapy. No clinical data are available on the use of a loading dose for adalimumab injection in children <6 years of age.
There are no data on the use of adalimumab injection in children <2 years for this indication.
Adults
Rheumatoid Arthritis
The recommended dose of Idacio for adult patients with rheumatoid arthritis is 40 mg administered every other week as a subcutaneous injection.
Psoriatic Arthritis
The recommended dose of Idacio for adult patients with psoriatic arthritis is 40 mg administered every other week as a subcutaneous injection.
For the rheumatoid arthritis and psoriatic arthritis indications, available data suggest that the clinical response is usually achieved within 12 weeks of treatment. Continued therapy should be carefully reconsidered in a patient not responding within this time period.
Ankylosing Spondylitis
The recommended dose of Idacio for patients with ankylosing spondylitis is 40 mg administered every other week via subcutaneous injection. Glucocorticoids, salicylates, nonsteroidal anti-inflammatory drugs, analgesics or disease modifying anti-rheumatic drugs can be continued during treatment with Idacio.
Crohn’s Disease
The recommended Idacio induction dose regimen for adult patients with Crohn’s disease is 160 mg at Week 0, followed by 80 mg at Week 2 administered by subcutaneous injection. The first dose of 160 mg can be given in one day (four 40 mg injections) or split over two consecutive days (two 40 mg injections each day). The second dose of 80 mg at Week 2 is given as two 40 mg injections in one day.
The recommended Idacio maintenance dose regimen for adult patients with Crohn’s disease is 40 mg every other week beginning at Week 4.
During treatment with Idacio, other concomitant therapies (e.g., corticosteroids and/or immunomodulatory agents) should be optimized.
For patients who experience a disease flare, dose escalation may be considered. See 14.5 Clinical Trials - Reference Biologic Drug, Crohn’s Disease, Study Results.
Some patients who have not responded by Week 4 (induction period) may benefit from continued maintenance therapy through Week 12. Available data suggest that the clinical response is usually achieved at Week 4 of treatment. Continued therapy should be carefully reconsidered in a patient not responding within this time period.
The use of adalimumab injection in Crohn’s disease has been evaluated up to one year in controlled clinical studies. In open-label studies, 510/1,594 patients were evaluated for three years, and 118/1,594 patients for at least five years.
Ulcerative Colitis
The recommended Idacio induction dose regimen for adult patients with ulcerative colitis is 160 mg at Week 0, followed by 80 mg at Week 2 administered by subcutaneous injection. The first dose of 160 mg can be given in one day (four 40 mg injections) or split over two consecutive days (two 40 mg injections each day). The second dose of 80 mg at Week 2 is given as two 40 mg injections in one day. Beginning at Week 4, continue with a dose of 40 mg every other week. Idacio should only be continued in patients who have responded during the first 8 weeks of therapy.
Aminosalicylates and/or corticosteroids may be continued during treatment with Idacio. Azathioprine and 6-mercaptopurine (6-MP) may be continued during treatment with Idacio if necessary (see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX).
During maintenance treatment, corticosteroids may be tapered in accordance with clinical practice guidelines.
Hidradenitis Suppurativa
The recommended Idacio initial dose for adult patients with hidradenitis suppurativa is 160 mg, followed by 80 mg two weeks later administered by subcutaneous injection. The first dose of 160 mg at Week 0 can be given in one day (four 40 mg injections) or split over two consecutive days (two 40 mg injections each day). The second dose of 80 mg at Week 2 is given as two 40 mg injections in one day.
The recommended Idacio maintenance dose regimen for adult patients with hidradenitis suppurativa is 40 mg every week beginning four weeks after the initial dose.
Antibiotics may be continued during treatment with Idacio if necessary.
In patients without any benefit after 12 weeks of treatment, continued therapy should be reconsidered.
Plaque Psoriasis
The recommended dose of Idacio for adult patients with psoriasis is an initial dose of 80 mg administered subcutaneously (two 40 mg injections), followed by 40 mg subcutaneously given every other week starting one week after the initial dose.
Continued therapy beyond 16 weeks should be carefully reconsidered in a patient not responding within this time period.
Uveitis
The recommended dose of Idacio for adult patients with non-infectious uveitis is an initial dose of 80 mg administered subcutaneously (two 40 mg injections), followed by 40 mg subcutaneously given every other week starting one week after the initial dose.
Idacio can be initiated in combination with corticosteroids and/or other non-biologic immunomodulatory agents. Corticosteroids may be tapered in accordance with clinical practice starting two weeks after initiating treatment with Idacio. There is limited experience with the initiation of treatment with adalimumab injection alone.
It is recommended that the benefit and risk of continued long-term treatment should be evaluated on a yearly basis.
4.4 Administration
Idacio is intended for use under the guidance and supervision of a physician. Patients may self-inject Idacio if their physician determines that it is appropriate and with medical follow-up, as necessary, after proper training in subcutaneous injection technique.
Idacio is only available as 40 mg pre-filled syringe and 40 mg auto-injector pen. Thus, it is not possible to administer Idacio to patients who require less than a full 40 mg dose.
Auto-injector (pen) or Prefilled Syringe
The solution in the auto-injector or prefilled syringe should be carefully inspected visually for particulate matter and discolouration prior to subcutaneous administration. If particulates and discolourations are noted, the product should not be used. Idacio does not contain preservatives; therefore, unused portions of drug remaining in the syringe or auto-injector should be discarded.
Auto-injector (pen)
Injection: 40 mg/0.8 mL of Idacio is provided by a single-dose auto-injector, containing a 1 mL prefilled glass syringe with a fixed 29-gauge, 12 mm thin wall steel needle protected by a rigid needle shield. The prefilled syringe is fitted with a pen-injector (Physioject®).
Prefilled Syringe
Injection: 40 mg/0.8 mL of Idacio is provided by a single-dose, 1 mL prefilled glass syringe with a fixed 29-gauge, 12 mm thin wall steel needle protected by a rigid needle shield. The prefilled syringe is fitted with a passive safety delivery system (Safe’n’Sound®), an anti-needle stick accessory.
Patients using the prefilled syringes, or the auto-injectors should be instructed to inject the full amount in the syringe or auto-injector (0.8 mL), which provides 40 mg of Idacio®, according to the directions provided in the PATIENT MEDICATION INFORMATION.
The auto-injector and prefilled syringe are not designed to deliver a portion of the full 40 mg dose and must not be used in pediatric patients who require <40 mg dose.
Injection sites should be rotated, and injections should never be given into areas where the skin is tender, bruised, red or hard. See PATIENT MEDICATION INFORMATION.
4.5 Missed Dose
Patients who miss a dose of Idacio should be advised to inject this missed dose as soon as they become aware of it, and then follow with their next scheduled dose.
5 OVERDOSAGE
The maximum tolerated dose of adalimumab injection has not been established in humans. Multiple doses up to 10 mg/kg have been administered to patients in clinical trials without evidence of dose-limiting toxicities. In case of overdosage, it is recommended that the patient be monitored for any signs or symptoms of adverse reactions or effects and appropriate symptomatic treatment instituted immediately.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/ Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Subcutaneous injection (s.c.) | Sterile solution (in either auto-injector or prefilled syringe) /40 mg adalimumab in 0.8 mL (50 mg/mL) | glacial acetic acid, trehalose, polysorbate 80, sodium chloride, Sodium hydroxide and Water for Injection. |
Idacio (adalimumab injection) is supplied as a sterile solution for subcutaneous administration in the following packaging configurations:
Auto-injector (pen)
Idacio is available as an auto-injector in a carton containing two dose trays. Each single use, disposable pen-injector is designed to enable self-injection of an entire single dose of drug product from a prefilled glass syringe with attached needle. Each pen-injector provides 40 mg of adalimumab injection in 0.8 mL sterile solution (50 mg/mL). All contents of the auto-injector carton do not contain natural rubber latex.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669).
Prefilled Syringe
Idacio is also available as a prefilled syringe in a carton containing two dose trays. Each dose contains a single-use syringe, assembled into an automatic needle retraction device with extended finger flanges. Each prefilled syringe provides 40 mg of adalimumab injection in 0.8 mL sterile solution (50 mg/mL). All contents of the prefilled syringe carton do not contain natural rubber latex.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
Concurrent Administration of Biologic DMARDs or TNF-Antagonists
Serious infections were seen in clinical studies with concurrent use of anakinra (an interleukin-1 antagonist) and another TNF-blocking agent, etanercept, with no added benefit compared to etanercept alone. Because of the nature of the adverse events seen with the combination of etanercept and anakinra, similar toxicities may also result from the combination of anakinra and other TNF-blocking agents. Therefore, the combination of Idacio (adalimumab injection) and anakinra is not recommended. See 9.4 Drug-Drug Interactions.
Concomitant administration of Idacio with other biologic DMARDs (e.g., anakinra and abatacept) or other TNF antagonists is not recommended based upon the increased risk for infections and other potential pharmacological interactions. See 9.4 Drug-Drug Interactions.
Switching Between Biological DMARDs
When switching from one biologic to another, patients should continue to be monitored for signs of infection.
Surgery
There is limited safety experience of surgical procedures in patients treated with adalimumab injection. The long half-life of adalimumab injection should be taken into consideration if a surgical procedure is planned. A patient who requires surgery while on Idacio should be closely monitored for infections, and appropriate actions should be taken. There is limited safety experience in patients undergoing arthroplasty while receiving adalimumab injection.
Carcinogenesis and Mutagenesis
Long-term animal studies of adalimumab have not been conducted to evaluate the carcinogenic potential or its effect on fertility. No clastogenic or mutagenic effects of adalimumab were observed in the in vivo mouse micronucleus test or the Salmonella-Escherichia coli (Ames) assay, respectively. See 16 NON-CLINICAL TOXICOLOGY - REFERENCE BIOLOGIC DRUG, Genotoxicity, In vitro Genotoxicity.
Cardiovascular
Patients with Congestive Heart Failure
Cases of worsening congestive heart failure (CHF) and new onset CHF have been reported with TNF-blockers. Cases of worsening CHF have also been observed with adalimumab injection. Adalimumab injection has not been formally studied in patients with CHF; however, in clinical trials of another TNF-blocker, a higher rate of serious CHF-related adverse events was observed. Physicians should exercise caution when using Idacio in patients who have heart failure and monitor them carefully. Idacio is contraindicated in moderate to severe heart failure (see 2 CONTRAINDICATIONS).
Gastrointestinal
Small Bowel Obstruction
Failure to respond to treatment for Crohn’s disease may indicate the presence of fixed fibrotic stricture that may require surgical treatment. Available data suggest that adalimumab injection does not worsen or cause strictures.
Hematologic
Rare reports of pancytopenia, including aplastic anemia, have been reported with TNF-blocking agents. Adverse events of the hematologic system, including medically significant cytopenia (e.g., thrombocytopenia, leukopenia) have been infrequently reported with adalimumab injection. The causal relationship of these reports to adalimumab injection remains unclear. All patients should be advised to seek immediate medical attention if they develop signs and symptoms suggestive of blood dyscrasias (e.g., persistent fever, bruising, bleeding, pallor) while on Idacio. Discontinuation of Idacio therapy should be considered in patients with confirmed significant hematologic abnormalities.
Hypersensitivity Reactions
Allergic reactions (e.g., allergic rash, anaphylactoid reaction, fixed drug reaction, non-specified drug reaction, urticaria) have been observed in approximately 1% of patients receiving adalimumab injection in clinical trials. See 8 ADVERSE REACTIONS. Reports of serious allergic reactions, including anaphylaxis, have been received following adalimumab injection administration. If an anaphylactic reaction or other serious allergic reactions occur, administration of Idacio should be discontinued immediately and appropriate therapy initiated.
Idacio pre-filled syringe and auto-injector are available with a 29 Gauge, 12 mm thin wall steel needle protected by a rigid needle shield. All contents of the prefilled syringe carton or auto-injector carton (including syringe or auto-injector, accessories and packaging) are latex-free. See 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
Immune
Autoimmunity
Treatment with adalimumab injection may result in the formation of autoantibodies and rarely, in the development of a lupus-like syndrome. If a patient develops symptoms suggestive of a lupus-like syndrome following treatment with Idacio, treatment should be discontinued. See 8.1 Adverse Reaction Overview, Autoantibodies.
Immunosuppression
The possibility exists for TNF-blocking agents, including adalimumab injection, to affect host defenses against infections and malignancies since TNF mediates inflammation and modulates cellular immune responses. In a study of 64 patients with rheumatoid arthritis who were treated with adalimumab injection, there was no evidence of depression of delayed-type hypersensitivity, depression of immunoglobulin levels, or change in enumeration of effector T-and B-cells and NK-cells, monocyte/macrophages, and neutrophils. The impact of treatment with adalimumab injection on the development and course of malignancies, as well as active and/or chronic infections, is not fully understood. See 7 WARNINGS AND PRECAUTIONS, Infections and Malignancies and 8.1 Adverse Reaction Overview, Infections and Malignancies.
Immunizations
In a randomized, double-blind, placebo-controlled study in 226 adult rheumatoid arthritis patients treated with adalimumab injection, antibody responses to concomitant pneumococcal and influenza vaccines were assessed. Protective antibody levels to the pneumococcal antigens were achieved by 86% of patients in the adalimumab injection group compared to 82% in the placebo group. A total of 37% of adalimumab injection-treated patients and 40% of placebo-treated patients achieved at least a 2-fold increase in antibody titer to at least three out of five pneumococcal antigens. In the same study, 98% of patients in the adalimumab injection group and 95% in the placebo group achieved protective antibody levels to the influenza antigens. A total of 52% of adalimumab injection-treated patients and 63% of placebo-treated patients achieved at least a 4-fold increase in antibody titer to at least two out of three influenza antigens.
It is recommended that pediatric patients, if possible, be brought up to date with all immunizations in agreement with current immunization guidelines prior to initiating Idacio therapy.
Patients on Idacio may receive concurrent vaccinations, except for live vaccines. No data are available on the secondary transmission of infection by live vaccines in patients receiving adalimumab injection.
Administration of live vaccines to infants exposed to adalimumab injection in utero is not recommended for five months following the mother’s last Idacio injection during pregnancy. See 7.1.1 Pregnant Women.
Infections
Tuberculosis
Tuberculosis, including reactivation and new onset of tuberculosis, has been reported in patients receiving adalimumab injection. Reports included cases of pulmonary and extrapulmonary (i.e., disseminated) tuberculosis. Before initiation, during and after treatment with adalimumab injection, patients should be evaluated for active and inactive (“latent”) tuberculosis infection with a tuberculin skin test. Treatment of latent tuberculosis infections should be initiated prior to therapy with Idacio. When tuberculin skin testing is performed for latent tuberculosis infection, an induration size of 5 mm or greater should be considered positive, even if vaccinated previously with Bacille Calmette-Guérin (BCG).
If active tuberculosis is diagnosed, Idacio therapy must not be initiated.
The possibility of undetected latent tuberculosis should be considered, especially in patients who have immigrated from or travelled to countries with a high prevalence of tuberculosis or who had close contact with a person with active tuberculosis. If latent infection is diagnosed, appropriate treatment must be started with anti-tuberculosis prophylactic treatment, in accordance with the Canadian Tuberculosis Standards and Centers for Disease Control and Prevention guidelines, before the initiation of Idacio. Use of anti-tuberculosis prophylactic treatment should also be considered before the initiation of Idacio in patients with several or significant risk factors for tuberculosis despite a negative test for tuberculosis and in patients with a past history of latent or active tuberculosis in whom an adequate course of treatment cannot be confirmed. The decision to initiate anti-tuberculosis therapy in these patients should only be made after taking into account both the risk for latent tuberculosis infection and the risks of anti-tuberculosis therapy. If necessary, consultation should occur with a physician with expertise in the treatment of tuberculosis.
Despite prophylactic treatment for tuberculosis, cases of reactivated tuberculosis have occurred in patients receiving adalimumab injection. Also, active tuberculosis has developed in patients receiving adalimumab injection whose screening for latent tuberculosis infection was negative, and some patients who have been successfully treated for active tuberculosis have redeveloped active tuberculosis while being treated with TNF-blocking agents.
Patients receiving Idacio should be monitored for signs and symptoms of active tuberculosis, particularly because tests for latent tuberculosis infection may be falsely negative. The risk of false negative tuberculin skin test results should be considered, especially in patients who are severely ill or immunocompromised. Patients should be instructed to seek medical advice if signs/symptoms suggestive of a tuberculosis infection (e.g., persistent cough, wasting/weight loss, low grade fever, listlessness) occur during or after therapy with Idacio, and physicians should monitor for signs and symptoms of active tuberculosis, including patients who are tuberculosis skin test negative.
Other Opportunistic Infections
Opportunistic infections, including invasive fungal infections, have been observed in patients receiving adalimumab injection. These infections are not consistently recognized in patients taking TNF-blockers and this has resulted in delays in appropriate treatment, sometimes resulting in fatal outcomes.
Patients taking TNF-blockers are more susceptible to serious fungal infections such as histoplasmosis, coccidioidomycosis, blastomycosis, aspergillosis, candidiasis, and other opportunistic infections. Those who develop fever, malaise, weight loss, sweats, cough, dyspnea, and/or pulmonary infiltrates, or other serious systemic illness with or without concomitant shock should promptly seek medical attention for a diagnostic evaluation.
For patients who reside or travel in regions where mycoses are endemic, invasive fungal infections should be suspected if they develop the signs and symptoms of possible systemic fungal infection. Patients are at risk of histoplasmosis and other invasive fungal infections and hence clinicians should consider empiric antifungal treatment until the pathogen(s) are identified. Antigen and antibody testing for histoplasmosis may be negative in some patients with active infection. When feasible, the decision to administer empiric antifungal therapy in these patients should be made in consultation with a physician with expertise in the diagnosis and treatment of invasive fungal infections and should take into account both the risk for severe fungal infection and the risks of antifungal therapy. Patients who develop a severe fungal infection are also advised to stop the TNF-blocker until infections are controlled.
Hepatitis B Virus (HBV) Reactivation
Very rare cases of hepatitis B virus (HBV) reactivation have been associated with anti-TNF therapy. Clinically active HBV infection occurred following a latency period ranging from 3 to 20 months after initiation of therapy. In the majority of cases, patients were also taking other immunosuppressive drugs, including methotrexate, azathioprine, and/or corticosteroids. Hence, establishing a causal relationship to anti-TNF agents is confounded by the presence of these other medications. Where outcome information was provided, most patients were reported to have improved after antiviral treatment and/or discontinuation of the anti-TNF agent. However, fatal outcomes have also occurred in reported cases. Patients at risk of HBV infection should be evaluated for prior evidence of HBV infection before initiating anti-TNF therapy. Those identified as chronic carriers (i.e., surface antigen positive) should be monitored for signs and symptoms of active HBV infection throughout the course of therapy and for several months following discontinuation of therapy. Reactivation of HBV is not unique to anti-TNF-alpha agents and has been reported with other immunosuppressive drugs.
Malignancies
In the controlled portions of clinical trials of some TNF-blocking agents, including adalimumab injection, more cases of malignancies have been observed among patients receiving those TNF-blockers compared to control patients.
In the controlled and uncontrolled open-label portions of clinical trials of adalimumab injection, the more frequently observed malignancies, other than lymphoma and non-melanoma skin cancer, were breast, colon, prostate, lung, and melanoma.
Cases of acute and chronic leukemia have been reported in association with post-marketing TNF-blocker use in rheumatoid arthritis and other indications. Patients with rheumatoid arthritis may be at a higher risk (up to 2-fold) than the general population for the development of leukemia, even in the absence of TNF-blocking therapy.
Malignancies in Pediatric Patients and Young Adults
Malignancies, some fatal, have been reported among children, adolescents and young adults who received treatment with TNF-blocking agents (i.e., including adalimumab injection). Approximately half the cases were lymphomas, including Hodgkin’s and non-Hodgkin’s lymphoma. The other cases represented a variety of different malignancies and included rare malignancies usually associated with immunosuppression and malignancies that are not usually observed in children and adolescents. The malignancies occurred after a median of 30 months of therapy (range 1 to 84 months). Most of the patients were receiving concomitant immunosuppressants. These cases were reported post-marketing and are derived from a variety of sources including registries and spontaneous post-marketing reports.
Post-marketing cases of hepatosplenic T-cell lymphoma (HSTCL), a rare type of T-cell lymphoma, have been reported in patients treated with TNF-blockers including adalimumab injection. These cases have had a very aggressive disease course and have been fatal. The majority of reported TNF-blocker cases have occurred in patients with Crohn’s disease or ulcerative colitis and the majority were in adolescent and young adult males. Almost all of these patients had received treatment with the immunosuppressants azathioprine or 6-mercaptopurine (6-MP) concomitantly with a TNF-blocker at or prior to diagnosis. It is uncertain whether the occurrence of HSTCL is related to use of a TNF-blocker or a TNF-blocker in combination with these other immunosuppressants. The potential risk with the combination of azathioprine or 6-mercaptopurine and Idacio should be carefully considered.
No malignancies were observed in pediatric patients aged 3 to 17 years with active JIA-associated chronic non-infectious anterior uveitis who were treated with adalimumab injection (n=90, randomized 2:1 to adalimumab injection: placebo) for up to 18 months in a clinical trial.
Treatment-emergent malignancies occurred in 2/480 adalimumab injection-treated UC patients in the double-blind controlled portion of two clinical trials (range of treatment duration from Weeks 0 to 52). The malignancies were squamous cell carcinoma and gastric cancer. Gastric cancer was considered serious and the patient discontinued as a result.
With current data it is not known if adalimumab injection treatment influences the risk for developing dysplasia or colon cancer. All patients with ulcerative colitis who are at risk for dysplasia or colon carcinoma (for example, patients with long-standing ulcerative colitis or primary sclerosing cholangitis), or who had a prior history of dysplasia or colon carcinoma should be screened for dysplasia at regular intervals before therapy and throughout their disease course. This evaluation should include colonoscopy and biopsies per local recommendations.
Lymphoma
In the controlled portions of clinical trials of all the TNF-blocking agents, more cases of lymphoma have been observed among patients receiving TNF-blockers compared to control patients.
However, for adalimumab injection, the occurrence of lymphoma was rare, and the follow-up period of placebo patients was shorter than for patients receiving TNF-antagonist therapy. The size of the control group and limited duration of the controlled portions of studies precludes the ability to draw firm conclusions. Furthermore, there is an increased background lymphoma risk in rheumatoid arthritis patients with long-standing, highly active, inflammatory disease, which complicates the risk estimation.
In combining the controlled and uncontrolled open-label portions of the 23 clinical trials in adult patients with rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, psoriasis, and uveitis, with a median duration of approximately 2.4 years, including 8764 patients and 27,196 patient-years of therapy, the observed rate of lymphomas (95% CI) is 1.2 [0.9, 1.7] per 1000 patient-years. This is approximately 3-fold higher than expected in the general population.
During the controlled and open-label periods of 14 trials with adalimumab injection, the overall standard incidence ratio (SIR) of malignancies was 0.99 [95% confidence interval (CI), 0.81 to 1.20]. With current knowledge in this area, a possible risk for development of lymphomas or other malignancies in patients treated with a TNF-antagonist cannot be excluded.
No studies have been conducted that include patients with a history of malignancy or that continue treatment in patients who develop malignancy while receiving adalimumab injection. Additional caution should be exercised when considering Idacio treatment in these patients.
Non-Lymphoma Malignancy
During the controlled portions of 21 adalimumab injection trials in adult patients with rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, psoriasis, and uveitis, malignancies, other than lymphoma and non-melanoma skin cancer, were observed at a rate (95 % CI) of 6.9 (4.4, 10.6) per 1,000 patient-years among 5196 adalimumab injection-treated patients versus a rate of 6.4 (3.5, 11.9) per 1,000 patient-years among 3347 control patients (median duration of treatment of 4.0 months for adalimumab injection-treated patients and 3.9 months for control-treated patients).
During the controlled portions of 21 adalimumab injection rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, psoriasis, and uveitis trials, the rate (95% CI) of non-melanoma skin cancers was 8.9 (6.1, 13.1) per 1,000 patient-years among adalimumab injection-treated patients and 3.2 (1.3, 7.7) per 1,000 patient-years among control patients. Of these skin cancers, squamous cell carcinomas occurred at rates (95% CI) of 2.7 (1.4, 5.5) per 1,000 patient-years among adalimumab injection-treated patients and 0.6 (0.1, 4.6) per 1,000 patient-years among control patients. The rate (95% CI) of lymphomas was 0.7 (0.2, 2.7) per 1,000 patient-years among adalimumab injection-treated patients and 0.6 (0.1, 4.6) per 1,000 patient-years among control patients.
The observed rate of malignancies, other than lymphoma and non-melanoma skin cancers, is approximately (95% CI) 8.5 (7.4, 9.7) per 1,000 patient years in the controlled portion of clinical trials and in ongoing and completed open-label extension studies. The observed rate of non-melanoma skin cancers is (95% CI) approximately 9.6 (8.5, 10.9) per 1,000 patient years, and the observed rate of lymphomas is (95% CI) approximately 1.3 (0.9, 1.8) per 1,000 patient years. The median duration of these studies is approximately 3.3 years and included 6276 adult patients who were on adalimumab injection for at least one year or who developed a malignancy within a year of starting therapy, representing over 26,044 patient years of therapy.
All patients, and in particular psoriasis patients with a medical history of extensive immunosuppressant therapy or psoriasis patients with a history of Psoralen Ultra-Violet A (PUVA) treatment should be examined for the presence of non-melanoma skin cancer prior to and during treatment with Idacio.
Monitoring and Laboratory Tests
There is no known interference between adalimumab injection and laboratory tests.
Neurologic
Use of TNF-blocking agents, including adalimumab injection, has been associated with rare cases of new onset or exacerbation of clinical symptoms and/or radiographic evidence of demyelinating disease, including multiple sclerosis, and optic neuritis, and peripheral demyelinating disease, including Guillain-Barré syndrome. Prescribers should exercise caution in considering the use of Idacio in patients with preexisting or recent onset central nervous system demyelinating disorders; discontinuation of Idacio should be considered if any of these disorders develop.
There is a known association between intermediate uveitis and central demyelinating disorders. Neurologic evaluation should be performed in patients with non-infectious intermediate uveitis prior to the initiation of Idacio therapy to assess for pre-existing central demyelinating disorders.
7.1 Special Populations
7.1.1 Pregnant Women
The extent of exposure in pregnancy during clinical trials is very limited, consisting only of individual cases.
An embryo-fetal perinatal developmental toxicity study has been performed in cynomolgus monkeys at dosages up to 100 mg/kg (266 times human area under the curve (AUC) when given 40 mg adalimumab subcutaneously with methotrexate every week, or 373 times when given 40 mg adalimumab subcutaneously without methotrexate) and has revealed no evidence of harm to the fetuses due to adalimumab. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction and developmental studies are not always predictive of human response, Idacio should be used during pregnancy only if clearly needed.
In a prospective cohort pregnancy exposure registry, conducted by the Organization of Teratology Information Specialists (OTIS)/MotherToBaby in the U.S. and Canada between 2004 and 2016, the risk of major birth defects in live-born infants was compared in 69 women with RA and 152 women with CD treated with adalimumab at least during the first trimester with 74 women with RA and 32 women with CD not treated with adalimumab during pregnancy. The proportion of major birth defects among live-born infants in the adalimumab-treated and untreated cohorts was 10% (8.7% RA, 10.5% CD) and 7.5% (6.8% RA, 9.4% CD), respectively.
No pattern of major birth defects was observed. This study cannot reliably establish whether there is an association between adalimumab and the risk for major birth defects because of methodological limitations of the registry, including small sample size, the voluntary nature of the study, and the non-randomized design.
Adalimumab may cross the placenta into the serum of infants born to women treated with adalimumab injection during pregnancy. Consequently, these infants may be at increased risk for infection. Administration of live vaccines to infants exposed to adalimumab in utero is not recommended for five months following the mother’s last adalimumab injection during pregnancy.
Labor and Delivery
There are no known effects of adalimumab injection on labor or delivery.
7.1.2 Breast-feeding
Limited information from case reports in the published literature indicates the presence of adalimumab in human milk at concentrations of 0.1 to 1% of the maternal serum level. Published data suggest that the systemic exposure of adalimumab to a breastfed infant is expected to be low because adalimumab is a large molecule and is degraded in the gastrointestinal tract. However, the effects of local exposure in the gastrointestinal tract are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for adalimumab and any potential adverse effects on the breastfed child from adalimumab or from the underlying maternal condition.
7.1.3 Pediatrics
Polyarticular Juvenile Idiopathic Arthritis
The efficacy and safety of adalimumab injection have been studied in pediatric patients aged 4 to 17 years (n=171) and 2 to 4 years (n=32). No overall differences were observed in the efficacy and safety between the two age groups. Adalimumab injection has not been studied in pediatric patients with polyarticular JIA less than 2 years of age or in pediatric patients with a weight below 10 kg.
Pediatric Uveitis
The efficacy and safety of adalimumab injection have been studied in pediatric patients with uveitis aged 2 to 17 years (n=90, randomized 2:1 to adalimumab injection: placebo). Very limited data are available for pediatric patients with uveitis between 2 and <3 years of age. Serious adverse events were more frequent in children 4 years of age and younger.
7.1.4 Geriatrics
A total of 519 rheumatoid arthritis patients 65 years of age and older, including 107 patients 75 years and older, received adalimumab injection in clinical Studies DE009, DE011, DE019 and DE031. No overall differences in effectiveness were observed between these patients and younger patients. The frequency of serious infection and malignancy among adalimumab injection-treated patients over age 65 was higher than for those under the age of 65. Because there is a higher incidence of infections and malignancies in the elderly population in general, caution should be used when treating the elderly.
8 ADVERSE REACTIONS
The adverse drug reaction profiles reported in clinical studies that compared Idacio to the reference biologic drug were comparable. The description of adverse reactions in this section is based on clinical experience with the reference biologic drug.
8.1 Adverse Reaction Overview
The most serious adverse reactions were (see 7 WARNINGS AND PRECAUTIONS):
- serious infections
- neurologic events
- malignancies
The most common adverse reaction in rheumatoid arthritis patients treated with adalimumab injection was injection site reactions. In controlled trials for rheumatoid arthritis, polyarticular JIA, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, psoriasis, and uveitis, 13% of patients treated with adalimumab injection developed injection site reactions (erythema and/or itching, hemorrhage, pain or swelling), compared to 7% of patients receiving control treatment. Most injection site reactions were described as mild and generally did not necessitate drug discontinuation.
The proportion of rheumatoid arthritis patients who discontinued treatment due to adverse events during the double-blind, placebo-controlled portion of rheumatoid arthritis Studies DE009, DE011, DE019 and DE031 was 7.0% for patients taking adalimumab injection, and 4.0% for placebo-treated patients. The most common adverse events leading to discontinuation of adalimumab injection were clinical flare reaction (0.7%), rash (0.3%) and pneumonia (0.3%).
Among patients with rheumatoid arthritis in placebo-controlled studies, deaths occurred in 8 of 1,380 (0.58%) adalimumab injection-treated patients compared to 1 of 690 (0.14%) placebo-treated patients. The rate of deaths in both treatment arms is less than expected in the normal population with a standard mortality ratio (SMR) of 0.87 (95% CI, 0.38, 1.72) in the adalimumab injection group and 0.25 (95% CI, 0.00, 1.37) in the placebo group.
In Study DE019, 553 patients were exposed to at least one dose of adalimumab injection and 202 patients completed 10 years of study. A total of 24 patients died during the 10-year exposure period to adalimumab injection (4 during the double-blind phase, 14 during the open-label extension phase and an additional 6 after study drug termination). Among the treatment-emergent deaths, the most common reasons were: 4 sepsis, 3 cancers and 3 respiratory system events. However, the total number of deaths was not higher than that calculated according to age-adjusted Standardized Mortality Rates.
Of the 553 patients, 23.0% discontinued due to an adverse event. The most common adverse events associated with discontinuation of study drug were pneumonia and breast cancer (n=5 each). Fatigue, pneumonia, cellulitis, and histoplasmosis (n=3 each) were the most common treatment-related adverse events leading to discontinuation of study drug.
In total, 49% of patients treated with adalimumab injection experienced a serious adverse event; 15.7% were considered at least possibly related to study drug. The most common serious adverse events were rheumatoid arthritis disease flare (n=35, 6.3%), pneumonia (n=26, 4.7%) and myocardial infarction (n=10, 1.8%); of these, only pneumonia was considered to be at least possibly related to study drug.
The most frequently reported treatment-emergent adverse events were infections (total n=448, 81%; serious n=85, 15.4%) and injection site reactions (n=115, 20.8%).
Adverse events of special interest among the 553 patients included 35 patients with malignancies other than non-melanoma skin cancer (including 5 cases of lymphoma); and 3 patients with tuberculosis. Serious adverse events of special interest included 5 patients each with pulmonary embolism and diverticulitis; 2 patients with multiple sclerosis; and 1 patient with hypersensitivity reaction.
Adalimumab injection has also been studied in 542 patients with early rheumatoid arthritis (disease duration less than three years) who were methotrexate naïve (Study DE013). No new safety signals were seen in this patient population compared to the safety profile seen in adalimumab injection Studies DE009, DE011, DE019 and DE031. In this study, deaths occurred in 5 of 542 (0.92%) adalimumab injection-treated patients compared to 1 of 257 (0.39%) methotrexate-treated patients. The rate of deaths in both treatment arms is less than expected in the normal population with a standard mortality ratio (SMR) of 0.57 (95% CI, 0.18, 1.32) in the adalimumab injection group and 0.22 (95% CI, 0.00, 1.23) in the methotrexate group.
Adalimumab injection has also been studied in 395 patients with psoriatic arthritis in two placebo-controlled studies and in an open-label extension study, in 393 patients with ankylosing spondylitis in two placebo-controlled studies, and in over 1,500 patients with Crohn’s disease in five placebo-controlled and two open-label extension studies. The safety profile for patients with psoriatic arthritis treated with adalimumab injection 40 mg every other week was similar to the safety profile seen in patients with rheumatoid arthritis, adalimumab injection Studies DE009, DE011, DE019, DE031 and DE013. During the controlled period of the psoriatic arthritis studies, no deaths occurred in the adalimumab injection treated or placebo-treated patients. During the psoriatic arthritis open-label study, two deaths occurred in 382 patients with 795.7 patient-years of exposure. The rate of deaths is less than expected in the normal population with a standard mortality ratio (SMR) of 0.39 (95% CI, 0.04, 1.43). Among patients enrolled in the psoriasis open-label study, 5 deaths occurred in 1,468 patients with 4,068.6 patient-years of exposure.
Adalimumab injection has also been studied in 1,010 patients with ulcerative colitis (UC) in two randomized, double-blind, placebo-controlled studies (M06-826, 8 weeks and M06-827, 52 weeks) and an open-label extension study. No new safety signals were seen in the ulcerative colitis patient population. During the controlled period of the ulcerative colitis studies, no deaths occurred in the adalimumab injection-treated or placebo-treated patients. In the overall adalimumab injection ulcerative colitis development program of 1,010 patients with 2007.4 patient years of exposure (622 patients were treated for >1 year), 2 treatment-emergent deaths occurred during the long-term open-label extension study (cardio-respiratory arrest and right ventricular failure). There were no new safety signals compared to the known safety profile of adalimumab injection in the double-blind controlled portion of ulcerative colitis studies.
Adalimumab injection has also been studied in 727 patients with hidradenitis suppurativa (HS) in three randomized, double-blind, placebo-controlled studies and an open-label extension study. No deaths were reported during the placebo-control periods. In the overall adalimumab injection hidradenitis suppurativa development program of 727 patients with 635.7 patient years of exposure (281 patients were treated for >1 year), 2 treatment-emergent deaths occurred (cardio-respiratory arrest and autoimmune pancreatitis). No new safety signals were seen in the hidradenitis suppurativa patient population.
Adalimumab injection has also been studied in 464 patients with uveitis in two randomized, double-masked, placebo-controlled studies (M10-877 and M10-880) and an open-label extension study (M11-327). No new safety signals for adalimumab injection were identified in the uveitis patient population. In the overall adalimumab injection adult uveitis development program of 464 adalimumab adult patients with 1308.2 patient-years of exposure, 6 treatment-emergent deaths were reported (chronic renal failure, aortic dissection/acute tamponade, B-cell lymphoma, brain abscess, pancreatic carcinoma, and accident). Two deaths occurred during the controlled period of the adult uveitis studies and 4 during the open-label extension study.
Autoantibodies
Patients had serum samples tested for autoantibodies at multiple time points in Studies DE009, DE011, DE019, DE031 and DE013. In those rheumatoid arthritis-controlled trials, 11.9% of patients treated with adalimumab injection and 8.1% of placebo-or active control-treated patients who had negative baseline antinuclear antibody (ANA) titers, developed positive titers at Week 24. Two patients out of 3441 treated with adalimumab injection developed clinical signs suggestive of new onset lupus-like syndrome. The patients improved following discontinuation of therapy. No patients developed lupus nephritis or central nervous system symptoms. The impact of long-term treatment with adalimumab injection on the development of autoimmune diseases is unknown.
Immunogenicity
Formation of anti-adalimumab injection antibodies is associated with increased clearance and reduced efficacy of adalimumab injection. There is no apparent correlation between the presence of anti-adalimumab antibodies and adverse events.
Pediatrics
In clinical trials with adalimumab injection therapy for polyarticular JIA, the proportion of patients achieving PedACR response was lower in anti-adalimumab injection antibody (AAA)-positive patients compared with AAA-negative patients.
In patients with polyarticular JIA who were 4 to 17 years (Study DE038), AAAs were identified in 27/171 subjects (15.8%) treated with adalimumab injection. In patients not given concomitant methotrexate, the incidence was 22/86 (25.6%), compared to 5/85 (5.9%) when adalimumab injection was used as add-on to methotrexate. In patients with polyarticular JIA who were 2 to <4 years of age or 4 years of age and older weighing <15 kg (Study M10-444), AAAs were identified in 7% (1/15) of patients, and the one patient was receiving concomitant methotrexate.
Adults
Rheumatoid arthritis patients in Studies DE009, DE011, and DE019 were tested at multiple time points for antibodies to adalimumab injection during the 6-to 12-month period. Approximately 5% (58/1062) of adult rheumatoid arthritis patients receiving adalimumab injection developed low-titer antibodies to adalimumab injection at least once during treatment, which were neutralizing in vitro. Patients treated with concomitant methotrexate had a lower rate of antibody development than patients on adalimumab injection monotherapy (1% versus 12%). With monotherapy, patients receiving every other week dosing may develop antibodies more frequently than those receiving weekly dosing. In patients receiving the recommended dosage of 40 mg every other week as monotherapy, the American College of Rheumatology (ACR 20) response was lower among anti-drug antibody-positive patients than among anti-drug antibody-negative patients. The long-term immunogenicity of adalimumab injections is unknown.
In patients with psoriatic arthritis, AAAs were identified in 38/376 patients (10%) treated with adalimumab injection. In patients not given concomitant methotrexate, the incidence was 13.5% (24/178 patients), compared to 7% (14/198 patients) when adalimumab injection was used as add-on to methotrexate.
In patients with ankylosing spondylitis, AAAs were identified in 17/204 patients (8.3%) treated with adalimumab injection. In patients not given concomitant methotrexate, the incidence was 16/185 (8.6%), compared to 1/19 (5.3%) when adalimumab injection was used as add-on to methotrexate.
In patients with Crohn’s disease, AAAs were identified in 2.6% (7/269) of patients receiving adalimumab injection.
In patients with ulcerative colitis, AAAs were identified in 5.0% (19/379) of patients receiving adalimumab injection. The clinical significance of this is unknown.
In patients with moderate to severe HS, AAAs were identified in 10/99 patients (10.1%) treated with adalimumab injection.
In patients with psoriasis, AAAs were identified in 77/920 patients (8.4%) treated with adalimumab injection monotherapy.
In patients with plaque psoriasis, the rate of antibody development with adalimumab injection monotherapy was 8%. However, due to the limitation of the assay conditions, antibodies to adalimumab injection could be detected only when serum adalimumab injection levels were <2 mcg/mL. Among these patients whose serum adalimumab injection levels were <2 mcg/mL (approximately 40% of total patients studied), the immunogenicity rate was 20.7%. In patients with plaque psoriasis on long-term adalimumab injection monotherapy who participated in a withdrawal and retreatment study and whose serum adalimumab injection levels were <2 mcg/mL (approximately 12% of total patients studied), the immunogenicity rate was 16%; the overall rate of antibody development prior to withdrawal was 1.9%, and 2.3% after retreatment.
In patients with non-infectious uveitis, AAAs were identified in 4.8% (12/249) of patients treated with adalimumab injection. However, due to the limitation of the assay conditions, antibodies to adalimumab injection could be detected only when serum adalimumab injection levels were <2 mcg/mL. Among the patients whose serum adalimumab injection levels were <2 mcg/mL (approximately 23% of total patients studied), the immunogenicity rate was 21.1%.
The data reflect the percentage of patients whose test results were considered positive for antibodies to adalimumab injection in an enzyme-linked immunosorbent assay (ELISA), and are highly dependent on the sensitivity and specificity of the assay. Additionally, the observed incidence of antibody positivity in an assay may be influenced by several factors including sample handling, timing of sample collection, concomitant medications, and underlying disease. For these reasons, comparison of the incidence of antibodies to adalimumab injection with the incidence of antibodies to other products may be misleading.
Infections
Pediatrics
In a controlled trial for polyarticular JIA (Study DE038), the rate of adverse events of infections was 238.5 per 100 patient-years in the adalimumab injection-treated JIA patients compared to 269.5 per 100 patient-years in control (placebo) treated patients, and the rate of serious infections was 6.1 per 100 patient-years in the adalimumab injection-treated JIA patients compared to 0 events in control (placebo) treated patients.
In an open-label trial for polyarticular JIA (Study M10-444), the rate of adverse events of infections was 206.2 per 100 patient-years while receiving adalimumab injection and the rate of serious infections was 6.7 per 100 patient-years while receiving adalimumab injection.
In a randomized controlled trial (SYCAMORE) for pediatric patients with active JIA-associated chronic non-infectious anterior uveitis, the rate of adverse events of infections was 236.4 per 100 patient-years (77%) for the adalimumab injection-treated group compared to 164.5 per 100 patient-years (40%) for the control (placebo) group. The rate of serious infections was 17.1 per 100 patient years (13%) in the adalimumab injection-treated uveitis patients compared to 0 events in control (placebo) treated patients.
Adults
In 23 controlled trials for rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, psoriasis, and uveitis, the rate of infection was 147.4 per 100 patient-years in 5630 adalimumab injection-treated patients and 142.7 per 100 patient-years in 3587 control-treated patients. The infections consisted primarily of nasopharyngitis, upper respiratory tract infection, and sinusitis. Most patients continued on adalimumab injection after the infection resolved.
The incidence of serious infections was 3.4 per 100 patient-years in adalimumab injection-treated patients and 3.2 per 100 patient-years in placebo and active control-treated patients.
In controlled and open-label studies with adalimumab injection, serious infections such as legionellosis (0.02 per 100 patient-years) have been reported. No cases of listeriosis have been reported and therefore, an estimated rate of 0.01 per 100 patient-years was calculated. Both infections have been reported spontaneously during the post-marketing period.
In controlled and open-label studies with adalimumab injection, serious infections (including fatal infections, which occurred rarely) have been reported, which include reports of tuberculosis (including miliary and extra-pulmonary locations) and invasive opportunistic infections (e.g., disseminated histoplasmosis, pneumocystis carinii pneumonia, and aspergillosis). Most of the cases of tuberculosis occurred within the first eight months after initiation of therapy and may reflect recrudescence of latent disease.
In the double-blind controlled portion of two clinical trials with adalimumab injection in patients with UC, serious infections occurred in 4/480 patients treated with adalimumab injection; they were appendicitis (n=1), anal abscess (n=1), catheter sepsis (n=1) and salmonellosis (n=1). Serious infections occurred in 8 placebo patients. Opportunistic infections occurred in 7/480 patients treated with adalimumab injection; they were candidiasis (n=3), oesophageal candidiasis (n=1) and oral candidiasis (n=3). Opportunistic infections occurred in 3 placebo patients.
In the double-blind controlled portion of three clinical trials with adalimumab injection in patients with HS, serious infections occurred in 4/419 patients treated with adalimumab injection; they were Escherichia infection (n=1), genital infection bacterial (n=1), infection (n=1), pilonidal cyst (n=1) and pyelonephritis (n=1). Serious infections occurred in 2/366 placebo patients.
In the double-masked controlled portion of two clinical trials with adalimumab injection in patients with uveitis, serious infections occurred in 7/250 (2.8 patients treated with adalimumab injection; they were pneumonia (n=2), and 1 each of bronchitis, pilonidal cyst, pneumonia Legionella, tuberculosis, upper respiratory tract infection and urinary tract infection. Serious infections occurred in 4/250 (1.6%) placebo patients. Opportunistic infections occurred in 7/250 patients treated with adalimumab injection; they were active tuberculosis (n=1), latent tuberculosis (n=4) and oral candidiasis (n=2). Latent tuberculosis occurred in 1 placebo-treated patient. In the open-label extension study (M11-327), the exposure-adjusted incidence rate of serious infections was increased in patients who received concomitant systemic corticosteroids and immunosuppressants in addition to treatment with adalimumab injection.
Injection Site Reactions
In controlled trials in adults and children, 13% of patients treated with adalimumab injection developed injection site reactions (erythema and/or itching, hemorrhage, pain or swelling), compared to 7% of patients receiving placebo or active control. Injection site reactions generally did not necessitate discontinuation of the medicinal product.
Malignancies
More cases of malignancy have been observed in adalimumab injection-treated patients compared to control-treated patients in clinical trials. See 7 WARNINGS AND PRECAUTIONS, Malignancies.
Neurologic Events
In 21 controlled trials for adult patients with rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn’s disease, ulcerative colitis, hidradenitis suppurativa, and psoriasis the rate of new onset or exacerbation of central nervous system demyelinating disease (including multiple sclerosis and optic neuritis) and peripheral demyelinating disease (including Guillain-Barre syndrome) was less than 0.4 per 1000 patient-years in 5,380 adalimumab injection-treated patients and 0.7 per 1000 patient-years in 3,337 control-treated patients. In controlled and open-label studies for adult patients treated with adalimumab injection, the rate (95% CI) of demyelinating diseases was 0.7 (0.4, 1.1) per 1000 patient-years. Demyelinating diseases were reported spontaneously during the post-marketing period.
In the double-masked controlled portion of two clinical trials with adalimumab injection in patients with uveitis, 1 (0.4%) case of multiple sclerosis was reported in 250 patients treated with adalimumab injection. In the adult uveitis development program including the open-label study, the rate (95% CI) of demyelinating diseases (i.e., multiple sclerosis and optic neuritis) was 5.4 (2.2, 11.0) per 1000 patient years.
See 7 WARNINGS AND PRECAUTIONS, Neurologic.
Psoriasis: New Onset and Worsening
Cases of new onset psoriasis, including pustular psoriasis and palmoplantar psoriasis, and cases of worsening of pre-existing psoriasis have been reported with the use of TNF-blockers, including adalimumab injection. Many of these patients were taking concomitant immunosuppressants (e.g., methotrexate, corticosteroids). Some of these patients required hospitalization. Most patients had improvement of their psoriasis following discontinuation of their TNF-blocker. Some patients have had recurrences of psoriasis when they were re-challenged with a different TNF-blocker. Discontinuation of Idacio should be considered for severe cases and those that do not improve or that worsen despite topical treatments.
Liver Enzyme Elevations
In controlled Phase 3 trials of adalimumab injection (40 mg subcutaneous every other week), in patients with RA and PsA with a control period duration ranging from 4 to 104 weeks, alanine aminotransferase (ALT) elevations ≥3 x ULN occurred in 3.7% of adalimumab injection-treated patients and 1.6% of control-treated patients. Since many of the patients in these trials were also taking medications that cause liver enzyme elevations (e.g., NSAIDS, methotrexate), the relationship between adalimumab injection and the liver enzyme elevations is not clear.
In controlled Phase 3 trials of adalimumab injection (initial doses of 160 mg and 80 mg, or 80 mg and 40 mg on Days 1 and 15, respectively, followed by 40 mg every other week), in adult patients with Crohn’s disease with a control period duration ranging from 4 to 52 weeks, ALT elevations ≥3 x ULN occurred in 0.9% of adalimumab injection-treated patients and 0.9% of control-treated patients.
In controlled Phase 3 trials of adalimumab injection (initial doses of 160 mg and 80 mg on Days 1 and 15, respectively, followed by 40 mg every other week), in patients with UC with a control period duration ranging from 1 to 52 weeks, ALT elevations ≥3 x ULN occurred in 1.5% of adalimumab injection-treated patients and 1.0% of control-treated patients. The incidence of ALT elevations ≥5 x ULN was 0.5% in adalimumab injection-treated patients and 0.2% in control-treated patients.
In controlled Phase 3 trials of adalimumab injection (initial dose of 80 mg then 40 mg every other week), in patients with plaque psoriasis with a control period duration ranging from 12 to 24 weeks, ALT elevations ≥3 x ULN occurred in 1.8% of adalimumab injection-treated patients and 1.8% of control-treated patients.
In controlled Phase 3 trials of adalimumab injection (40 mg every other week), in patients with ankylosing spondylitis with a control period of 12 to 24 weeks, ALT elevations ≥3 x ULN occurred in 2.4% of adalimumab injection-treated patients and 0.7% of control-treated patients.
In controlled trials of adalimumab injection (initial doses of 160 mg at Week 0 and 80 mg at Week 2, followed by 40 mg every week starting at Week 4), in adult patients with hidradenitis suppurativa with a control period duration ranging from 12 to 16 weeks, ALT elevations ≥3 x ULN occurred in 0.3% of adalimumab injection-treated patients and 0.6% of control-treated patients.
In controlled Phase 3 trials of adalimumab injection (initial doses of 80 mg at Week 0 followed by 40 mg every other week starting at Week 1) in patients with adult uveitis with an exposure of 165.4 patient-years and 119.8 patient-years in adalimumab injection-treated and control-treated patients, respectively, ALT elevations ≥3 x ULN occurred in 2.4% of adalimumab injection-treated patients and 2.4% of control-treated patients.
Across all adult indications in clinical trials, patients with raised ALT were asymptomatic and in most cases elevations were transient and resolved on continued treatment. However, there have been very rare post-marketing reports of severe hepatic reactions including liver failure as well as less severe liver disorders that may precede liver failure, such as hepatitis including autoimmune hepatitis, in patients receiving TNF blockers, including adalimumab. The causal relationship to adalimumab injection treatment remains unclear.
Concurrent treatment with azathioprine/6-mercaptopurine
In adult Crohn’s disease studies, higher incidences of malignant and serious infection-related adverse events were seen with the combination of adalimumab injection and azathioprine/6-mercaptopurine compared with adalimumab injection alone.
8.2 Clinical Trial Adverse Reactions
Because clinical trials are conducted under very specific conditions, the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Rheumatoid Arthritis
Description of Data Sources
The data described below reflect exposure to adalimumab injection in 3,046 patients, including more than 2,000 patients exposed for six months, and more than 1,500 exposed for more than one year (Studies DE009, DE011, DE019, DE031 and DE013). Adalimumab injection was studied in placebo-controlled trials and in long-term follow-up studies for up to 60 months duration in patients with moderately to severely active rheumatoid arthritis who had failed previous DMARD therapy; the mean age was 54 years, 77% were female and 91% Caucasian (Studies DE009, DE011, DE019, DE031). A further study (Study DE013) was in patients with recently diagnosed rheumatoid arthritis who had not previously been treated with methotrexate. Most patients received adalimumab injection 40 mg every other week.
Relative Frequency of Adverse Drug Reactions
Table 4 summarizes adverse drug reactions reported at a rate of at least 1% in patients treated with adalimumab injection 40 mg every other week, as well as all doses of adalimumab injection tested, compared to placebo or methotrexate (Study DE013). Adverse reaction rates in patients treated with adalimumab injection 40 mg weekly were similar to rates in patients treated with adalimumab injection every other week. In Study DE019, the types and frequencies of adverse drug reactions in the 10-year open-label extension were similar to those observed in the one-year double-blind portion.
Table 4 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During the Control Period in Rheumatoid Arthritis Studies (Studies DE009, DE011, DE019, DE031, DE013)
| System Organ Class (SOC) | Adalimumab injection 40 mg s.c. eow | Adalimumab injection (all adalimumab injection) | Placebo (not Study DE013) | MTX (Study DE013) | ||||
|---|---|---|---|---|---|---|---|---|
| System Organ Class (SOC) | Adalimumab injection 40 mg s.c. eow | Adalimumab injection (all adalimumab injection) | Placebo (not Study DE013) | MTX (Study DE013) | ||||
| System Organ Class (SOC) | Adalimumab injection 40 mg s.c. eow | Adalimumab injection (all adalimumab injection) | Placebo (not Study DE013) | MTX (Study DE013) | ||||
N=1247 n (%) | N=1922 n (%) | N=690 n (%) | N=257 n (%) | |||||
N=1247 n (%) | N=1922 n (%) | N=690 n (%) | N=257 n (%) | |||||
N=1247 n (%) | N=1922 n (%) | N=690 n (%) | N=257 n (%) | |||||
| Gastrointestinal Disorders | ||||||||
| Nausea | 80 (6.4) | 112 (5.8) | 12 (1.7) | 33 (12.8) | ||||
| Diarrhea | 47 (3.8) | 60 (3.1) | 17 (2.5) | 18 (7.0) | ||||
| Abdominal pain | 22 (1.8) | 29 (1.5) | 5 (0.7) | 3 (1.2) | ||||
| Abdominal pain upper | 20 (1.6) | 25 (1.3) | 0 (0.0) | 13 (5.1) | ||||
| Mouth ulceration | 17 (1.4) | 24 (1.2) | 5 (0.7) | 12 (4.7) | ||||
| Dyspepsia | 14 (1.1) | 21 (1.1) | 4 (0.6) | 7 (2.7) | ||||
| Vomiting | 16 (1.3) | 20 (1.0) | 5 (0.7) | 6 (2.3) | ||||
| General Disorders and Administration Site Conditions | ||||||||
| Injection site irritation | 74 (5.9) | 122 (6.3) | 61 (8.8) | 3 (1.2) | ||||
| Injection site reaction | 49 (3.9) | 67 (3.5) | 3 (0.4) | 2 (0.8) | ||||
| Injection site pain | 36 (2.9) | 63 (3.3) | 24 (3.5) | 6 (2.3) | ||||
| Injection site erythema | 36 (2.9) | 60 (3.1) | 2 (0.3) | 1 (0.4) | ||||
| Fatigue | 37 (3.0) | 58 (3.0) | 7 (1.0) | 9 (3.5) | ||||
| Injection site rash | 17 (1.4) | 22 (1.1) | 2 (0.3) | 0 (0.0) | ||||
| Influenza-like illness | 15 (1.2) | 21 (1.1) | 2 (0.3) | 8 (3.1) | ||||
| Pyrexia | 13 (1.0) | 20 (1.0) | 1 (0.1) | 6 (2.3) | ||||
| Infections and Infestations | ||||||||
| Nasopharyngitis | 61 (4.9) | 95 (4.9) | 10 (1.5) | 28 (10.9) | ||||
| Upper respiratory infection | 72 (5.8) | 93 (4.8) | 15 (2.2) | 17 (6.6) | ||||
| Sinusitis | 46 (3.7) | 55 (2.9) | 17 (2.5) | 4 (1.6) | ||||
| Herpes simplex | 33 (2.6) | 48 (2.5) | 6 (0.9) | 5 (1.9) | ||||
| Urinary tract infection | 31 (2.5) | 44 (2.3) | 6 (0.9) | 7 (2.7) | ||||
| Bronchitis | 19 (1.5) | 29 (1.5) | 8 (1.2) | 9 (3.5) | ||||
| Herpes zoster | 17 (1.4) | 23 (1.2) | 8 (1.2) | 2 (0.8) | ||||
| Influenza | 16 (1.3) | 21 (1.1) | 7 (1.0) | 5 (1.9) | ||||
| Pneumonia | 17 (1.4) | 21 (1.1) | 3 (0.4) | 1 (0.4) | ||||
| Investigations | ||||||||
| Lymphocyte count decreased | 11 (0.9) | 38 (2.0) | 11 (1.6) | 1 (0.4) | ||||
| Alanine aminotransferase increased | 27 (2.2) | 33 (1.7) | 4 (0.6) | 9 (3.5) | ||||
| Liver function test abnormal | 19 (1.5) | 22 (1.1) | 4 (0.6) | 7 (2.7) | ||||
| Musculoskeletal and Connective Tissue Disorders | ||||||||
| Rheumatoid arthritis | 11 (0.9) | 28 (1.5) | 7 (1.0) | 2 (0.8) | ||||
| Nervous System Disorders | ||||||||
| Headache | 75 (6.0) | 124 (6.5) | 14 (2.0) | 14 (5.4) | ||||
| Dizziness | 23 (1.8) | 32 (1.7) | 6 (0.9) | 3 (1.2) | ||||
| Respiratory, Thoracic and Mediastinal Disorders | ||||||||
| Pharyngolaryngeal pain | 33 (2.6) | 44 (2.3) | 9 (1.3) | 7 (2.7) | ||||
| Cough | 31 (2.5) | 42 (2.2) | 4 (0.6) | 9 (3.5) | ||||
| Skin and Subcutaneous Tissue Disorders | ||||||||
| Rash | 44 (3.5) | 66 (3.4) | 9 (1.3) | 8 (3.1) | ||||
| Pruritus | 28 (2.2) | 43 (2.2) | 4 (0.6) | 5 (1.9) | ||||
| Alopecia | 22 (1.8) | 28 (1.5) | 2 (0.3) | 6 (2.3) | ||||
| Rash pruritic | 14 (1.1) | 22 (1.1) | 0 (0.0) | 3 (1.2) | ||||
| Definition(s): s.c.=subcutaneous; eow=every other week | ||||||||
Psoriatic Arthritis
Table 5 summarizes adverse drug reactions reported in placebo-controlled and open-label studies at a rate of at least 1% in psoriatic arthritis patients treated with adalimumab injection 40 mg every other week.
Table 5 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During the Control and Open-Label Periods in Psoriatic Arthritis Studies (Studies M02-518, M02-570, and M02-537)
| System Organ Class (SOC) | Double-Blind Study | Open-Label Study | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| System Organ Class (SOC) | Double-Blind Study | Open-Label Study | |||||||||
Placebo 40 mg s.c. eow | Adalimumab injection 40 mg s.c. eow | Adalimumab injection 40 mg s.c. eow | |||||||||
Placebo 40 mg s.c. eow | Adalimumab injection 40 mg s.c. eow | Adalimumab injection 40 mg s.c. eow | |||||||||
N=211 n (%) | N=382 n (%) | N=202 n (%) | |||||||||
N=211 n (%) | N=382 n (%) | N=202 n (%) | |||||||||
| Gastrointestinal Disorders | |||||||||||
| Nausea | 2 (0.9) | 2 (1.0) | 3 (0.8) | ||||||||
| General Disorders and Administration Site Conditions | |||||||||||
| Injection site reaction | 5 (2.4) | 11 (5.4) | 21 (5.5) | ||||||||
| Injection site pain | 8 (3.8) | 8 (4.0) | 2 (0.5) | ||||||||
| Injection site erythema | 0 (0.0) | 4 (2.0) | 2 (0.5) | ||||||||
| Injection site burning | 4 (1.9) | 4 (2.0) | 4 (1.0) | ||||||||
| Fatigue | 5 (2.4) | 0 (0.0) | 4 (1.0) | ||||||||
| Infections and Infestations | |||||||||||
| Upper respiratory infection | 7 (3.3) | 8 (4.0) | 17 (4.5) | ||||||||
| Herpes simplex | 3 (1.4) | 6 (3.0) | 7 (1.8) | ||||||||
| Skin fungal infection NOS | 0 (0.0) | 3 (1.5) | - | ||||||||
| Pharyngitis | 1 (0.5) | 2 (1.0) | 4 (1.0) | ||||||||
| Sinusitis | 4 (1.9) | 2 (1.0) | 12 (3.1) | ||||||||
| Urinary tract infection | 0 (0.0) | 2 (1.0) | 6 (1.6) | ||||||||
| Bronchitis | 1 (0.5) | 1 (0.5) | 5 (1.3) | ||||||||
| Nasopharyngitis | 2 (0.9) | 1 (0.5) | 8 (2.1) | ||||||||
| Influenza | 2 (0.9) | 0 (0.0) | 5 (1.3) | ||||||||
| Investigations | |||||||||||
| Liver function tests abnormal | 1 (0.5) | 2 (1.0) | 5 (1.3) | ||||||||
| Nervous System Disorders | |||||||||||
| Headache | 5 (2.4) | 5 (2.5) | 5 (1.3) | ||||||||
| Paresthesia | 1 (0.5) | 3 (1.5) | 2 (0.5) | ||||||||
| Respiratory, Thoracic, and Mediastinal Disorders | |||||||||||
| Rhinitis NOS | 0 (0.0) | 3 (1.5) | 3 (0.8) | ||||||||
| Skin and Subcutaneous Tissue Disorders | |||||||||||
| Erythema | 0 (0.0) | 3 (1.5) | - | ||||||||
| Definition(s): s.c.=subcutaneous; eow=every other week | |||||||||||
Ankylosing Spondylitis
Adalimumab injection has been studied in 393 patients with ankylosing spondylitis in two placebo-controlled studies. The safety profile for patients with ankylosing spondylitis treated with adalimumab injection 40 mg every other week was similar to the safety profile seen in patients with rheumatoid arthritis, adalimumab injection Studies DE009, DE011, DE019, and DE031. Table 6 summarizes adverse drug reactions reported at a rate of at least 1% in ankylosing spondylitis patients treated with adalimumab injection 40 mg every other week compared to placebo.
Table 6 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During the Control Period in Ankylosing Spondylitis Studies (Studies M03-607 and M03-606)
| System Organ Class (SOC) | Adalimumab injection 40 mg s.c. eow | Placebo | |
|---|---|---|---|
N=246 n (%) | N=151 n (%) | ||
| General Disorders and Administration Site Conditions | |||
| Fatigue | 5 (2.0) | 3 (2.0) | |
| Injection site erythema | 5 (2.0) | 1 (0.7) | |
| Injection site irritation | 4 (1.6) | 2 (1.3) | |
| Injection site pain | 6 (2.4) | 3 (2.0) | |
| Injection site reaction | 8 (3.3) | 1 (0.7) | |
| Infections and Infestations | |||
| Nasopharyngitis | 8 (3.3) | 0 (0.0) | |
| Upper respiratory tract infection | 5 (2.0) | 2 (1.3) | |
| Nervous System Disorders | |||
| Dizziness | 3 (1.2) | 3 (2.0) | |
| Headache | 11 (4.5) | 4 (2.6) | |
| Skin and Subcutaneous Tissue Disorders | |||
| Eczema | 3 (1.2) | 1 (0.7) | |
| Pruritus | 4 (1.6) | 1 (0.7) | |
| Pruritus generalized | 3 (1.2) | 0 (0.0) | |
| Rash | 4 (1.6) | 1 (0.7) | |
| Urticaria | 3 (1.2) | 0 (0.0) | |
| Definition(s): s.c.=subcutaneous; eow=every other week | |||
Crohn’s Disease
Adalimumab injection has been studied in over 1,500 patients with Crohn’s disease in five placebo-controlled and two open-label extension studies. The safety profile for patients with Crohn’s disease treated with adalimumab injection was similar to the safety profile seen in patients with rheumatoid arthritis including the safety profile for patients in placebo-controlled Study M05-769. No new safety signals occurred during the open-label long-term studies with adalimumab injection exposure up to five years. The safety profile of adalimumab injection in Crohn’s disease remains unaltered.
Table 7 and Table 8 summarize adverse drug reactions reported at a rate of at least 1% in Crohn’s disease patients treated with adalimumab injection in induction and maintenance studies, respectively.
Table 7 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During Administration of Induction Study Medications in Crohn’s Disease Studies (Studies M02-403 and M04-691)
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Adalimumab injection 80/40 mg | Placebo | ||||
|---|---|---|---|---|---|---|---|
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Adalimumab injection 80/40 mg | Placebo | ||||
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Adalimumab injection 80/40 mg | Placebo | ||||
N=235 n (%) | N=75 n (%) | N=240 n (%) | |||||
N=235 n (%) | N=75 n (%) | N=240 n (%) | |||||
N=235 n (%) | N=75 n (%) | N=240 n (%) | |||||
| Eye Disorders | |||||||
| Corneal pigmentation | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Visual disturbance | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Gastrointestinal Disorders | |||||||
| Abdominal pain | 5 (2.1) | 0 (0.0) | 2 (0.8) | ||||
| Abdominal pain lower | 3 (1.3) | 0 (0.0) | 0 (0.0) | ||||
| Change of bowel habit | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Cheilitis | 0 (0.0) | 1 (1.3) | 1 (0.4) | ||||
| Constipation | 2 (0.9) | 1 (1.3) | 3 (1.3) | ||||
| Crohn’s disease | 2 (0.9) | 1 (1.3) | 3 (1.3) | ||||
| Flatulence | 3 (1.3) | 0 (0.0) | 0 (0.0) | ||||
| Nausea | 6 (2.6) | 0 (0.0) | 4 (1.7) | ||||
| Vomiting | 1 (0.4) | 1 (1.3) | 3 (1.3) | ||||
| General Disorders and Administration Site Conditions | |||||||
| Asthenia | 0 (0.0) | 1 (1.3) | 1 (0.4) | ||||
| Chills | 0 (0.0) | 2 (2.7) | 1 (0.4) | ||||
| Fatigue | 2 (0.9) | 1 (1.3) | 10 (4.2) | ||||
| Influenza like illness | 0 (0.0) | 2 (2.7) | 2 (0.8) | ||||
| Injection site bruising | 5 (2.1) | 1 (1.3) | 1 (0.4) | ||||
| Injection site erythema | 4 (1.7) | 0 (0.0) | 0 (0.0) | ||||
| Injection site irritation | 19 (8.1) | 8 (10.7) | 14 (5.8) | ||||
| Injection site pain | 6 (2.6) | 4 (5.3) | 9 (3.8) | ||||
| Injection site pruritus | 3 (1.3) | 0 (0.0) | 0 (0.0) | ||||
| Injection site reaction | 11 (4.7) | 5 (6.7) | 6 (2.5) | ||||
| Pain | 2 (0.9) | 1 (1.3) | 3 (1.3) | ||||
| Pyrexia | 3 (1.3) | 3 (1.3) | 3 (1.3) | ||||
| Infections and Infestations | |||||||
| Staphylococcal infection | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Investigations | |||||||
| Double stranded DNA antibody | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| White blood cell count increased | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Metabolism and Nutrition Disorders | |||||||
| Hypokalemia | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Musculoskeletal and Connective Tissue Disorders | |||||||
| Arthralgia | 3 (1.3) | 1 (1.3) | 2 (0.8) | ||||
| Back pain | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Muscle spasms | 0 (0.0) | 1 (1.3) | 1 (0.4) | ||||
| Pain in extremity | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Nervous System Disorders | |||||||
| Dizziness | 3 (1.3) | 0 (0.0) | 2 (0.8) | ||||
| Headache | 8 (3.4) | 2 (2.7) | 7 (2.9) | ||||
| Restless legs syndrome | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Reproductive System and Breast Disorders | |||||||
| Genital pruritus female | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Eczema | 1 (0.4) | 1 (1.3) | 0 (0.0) | ||||
| Erythema | 1 (0.4) | 1 (1.3) | 1 (0.4) | ||||
| Hyperhidrosis | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Onychorrhexis | 0 (0.0) | 1 (1.3) | 0 (0.0) | ||||
| Pruritus | 1 (0.4) | 0 (0.0) | 4 (1.7) | ||||
| Rash | 2 (0.9) | 2 (2.7) | 1 (0.4) | ||||
| Rash maculo-papular | 1 (0.4) | 1 (1.3) | 0 (0.0) | ||||
| Rash pruritic | 0 (0.0) | 1 (1.3) | 1 (0.4) | ||||
Table 8 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During Administration of Blinded Study Maintenance Medications in Crohn’s Disease Studies (Studies M02-404 and M02-433) Adalimumab injection
| System Organ Class (SOC) | Adalimumab injection 40 mg s.c. eow, 40 mg ew | Placebo | |
|---|---|---|---|
N=554 n (%) | N=279 n (%) | ||
| Gastrointestinal Disorders | |||
| Abdominal pain | 7 (1.3) | 4 (1.4) | |
| Crohn's disease | 9 (1.6) | 9 (3.2) | |
| Diarrhea | 7 (1.3) | 1 (0.4) | |
| Nausea | 9 (1.6) | 5 (1.8) | |
| General Disorders and Administration Site Conditions | |||
| Fatigue | 10 (1.8) | 1 (0.4) | |
| Injection site bruising | 6 (1.1) | 1 (0.4) | |
| Injection site erythema | 10 (1.8) | 0 (0.0) | |
| Injection site irritation | 18 (3.2) | 2 (0.7) | |
| Injection site pain | 8 (1.4) | 2 (0.7) | |
| Injection site reaction | 26 (4.7) | 1 (0.4) | |
| Pyrexia | 7 (1.3) | 5 (1.8) | |
| Infections and Infestations | |||
| Herpes simplex | 6 (1.1) | 4 (1.4) | |
| Nasopharyngitis | 8 (1.4) | 2 (0.7) | |
| Rhinitis | 7 (1.3) | 1 (0.4) | |
| Musculoskeletal and Connective Tissue Disorders | |||
| Arthralgia | 9 (1.6) | 2 (0.7) | |
| Nervous System Disorders | |||
| Headache | 19 (3.4) | 6 (2.2) | |
| Skin and Subcutaneous Tissue Disorders | |||
| Rash | 11 (2.0) | 5 (1.8) | |
| Definition(s): s.c.=subcutaneous; ew=every week; eow=every other week | |||
Ulcerative Colitis
Adalimumab injection has been studied in 1,010 patients with ulcerative colitis (UC) in two placebo-controlled studies and one open-label extension study. The safety profile for patients with UC treated with adalimumab injection was similar to the safety profile observed in patients with Crohn’s Disease.
Table 9 and Table 10 summarize adverse drug reactions reported at a rate of at least 1% in ulcerative colitis disease patients treated with adalimumab injection during induction and maintenance periods, respectively.
Table 9 Number and Percentage of Subjects ≥1% Reporting Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During Administration of Induction Study Medications in Ulcerative Colitis Studies (Studies M06-826 and M06-827)
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Adalimumab injection 80/40 mg | Placebo | ||
|---|---|---|---|---|---|
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Adalimumab injection 80/40 mg | Placebo | ||
N=480 n (%) | N=130 n (%) | N=483 n (%) | |||
N=480 n (%) | N=130 n (%) | N=483 n (%) | |||
| Gastrointestinal Disorders | 17 (3.5) | 7 (5.4) | 27 (5.6) | ||
| Abdominal pain | 0 (0.0) | 2 (1.5) | 2 (0.4) | ||
| Colitis Ulcerative | 7 (1.5) | 2 (1.5) | 8 (1.7) | ||
| Nausea | 6 (1.3) | 1 (0.8) | 7 (1.4) | ||
| General Disorders and Administration Site Conditions | 44 (9.2) | 8 (6.2) | 34 (7.0) | ||
| Fatigue | 9 (1.9) | 1 (0.8) | 7 (1.4) | ||
| Influenza like illness | 1 (0.2) | 1 (0.8) | 5 (1.0) | ||
| Injection site erythema | 8 (1.7) | 1 (0.8) | 2 (0.4) | ||
| Injection Site Haematoma | 2 (0.4) | 2 (1.5) | 0 (0.0) | ||
| Injection site pain | 11 (2.3) | 2 (1.5) | 11 (2.3) | ||
| Injection site pruritus | 6 (1.3) | 1 (0.8) | 1 (0.2) | ||
| Injection site reaction | 5 (1.0) | 1 (0.8) | 2 (0.4) | ||
| Pyrexia | 3 (0.6) | 1 (0.8) | 7 (1.4) | ||
| Infections and Infestations | 19 (4.0) | 7 (5.4) | 24 (5.0) | ||
| Herpes simplex | 0 (0.0) | 2 (1.5) | 0 (0.0) | ||
| Nasopharyngitis | 5 (1.0) | 1 (0.8) | 4 (0.8) | ||
| Oral herpes | 2 (0.4) | 2 (1.5) | 2 (0.4) | ||
| Nervous System Disorders | 14 (2.9) | 2 (1.5) | 25 (5.2) | ||
| Headache | 7 (1.5) | 2 (1.5) | 20 (4.1) | ||
| Pyschiatric Disorders | 1 (0.2) | 2 (1.5) | 4 (0.8) | ||
| Anxiety | 0 (0.0) | 2 (1.5) | 0 (0.0) | ||
| Skin and Subcutaneous Tissue Disorders | 19 (4.0) | 8 (6.2) | 17 (3.5) | ||
| Erythema | 5 (1.0) | 2 (1.5) | 1 (0.2) | ||
| Rash | 2 (0.4) | 2 (3.1) | 1 (0.2) | ||
Table 10 Number and Percentage of Subjects ≥1% Reporting Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During the Double-blind Induction and Maintenance Periods of Ulcerative Colitis Studies (Studies M06-826 and M06-827)
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Placebo | ||
| System Organ Class (SOC) | Adalimumab injection 160/80 mg | Placebo | ||
N=480 n (%) | N=483 n (%) | |||
N=480 n (%) | N=483 n (%) | |||
| Gastrointestinal Disorders | 31 (6.5) | 36 (7.5) | ||
| Colitis ulcerative | 12 (2.5) | 14 (2.9) | ||
| Nausea | 9 (1.9) | 9 (1.9) | ||
| General Disorders And Administration Site Conditions | 64 (13.3) | 38 (7.9) | ||
| Fatigue | 10 (2.1) | 8 (1.7) | ||
| Influenza like illness | 3 (0.6) | 5 (1.0) | ||
| Injection site erythema | 15 (3.1) | 3 (0.6) | ||
| Injection site pain | 11 (2.3) | 12 (2.5) | ||
| Injection site pruritus | 9 (1.9) | 2 (0.4) | ||
| Injection site reaction | 11 (2.3) | 2 (0.4) | ||
| Injection site swelling | 5 (1.0) | 0 (0.0) | ||
| Malaise | 5 (1.0) | 2 (0.4) | ||
| Oedema peripheral | 5 (1.0) | 1 (0.2) | ||
| Infections and Infestations | 40 (8.3) | 42 (8.7) | ||
| Influenza | 0 (0.0) | 5 (1.0) | ||
| Nasopharyngitis | 9 (1.9) | 7 (1.4) | ||
| Upper respiratory tract infection | 5 (1.0) | 7 (1.4) | ||
| Musculoskeletal and Connective Tissue Disorders | 12 (2.5) | 12 (2.5) | ||
| Arthralgia | 5 (1.0) | 4 (0.8) | ||
| Nervous System Disorders | 19 (4.0) | 28 (5.8) | ||
| Headache | 10 (2.1) | 22 (4.6) | ||
| Skin and Subcutaneous Tissue Disorders | 38 (7.9) | 29 (6.0) | ||
| Erythema | 6 (1.3) | 2 (0.4) | ||
| Pruritus | 5 (1.0) | 5 (1.0) | ||
| Rash | 7 (1.5) | 5 (1.0) | ||
Serious adverse events resulting in hospitalizations were reported by 18% (67/379) in the adalimumab injection-treated patients compared to 26% (56/214) in the placebo group adjusted for patient years at risk.
During the double-blind controlled clinical trials, the most common (≥5%) adverse drug reactions in subjects receiving adalimumab injection 160/80 during induction were ulcerative colitis (n=35, 7.3%) and nasopharyngitis (n=26, 5.4%), and during maintenance were ulcerative colitis (n=38, 16.2%), nasopharyngitis (n=26, 11.1%), abdominal pain (n=17, 7.3%), and arthralgia (n=17, 7.3%). There were 2/480 adalimumab injection-treated patients who experienced severe leukopenia of which one case was serious. The patient with serious leukopenia, which was considered secondary to 6-MP, had an associated viral infection.
During the double-blind controlled clinical trials, the most common serious adverse event occurring in >1 patient more often in the adalimumab injection-treated patients compared to placebo when adjusted for exposure was deep vein thrombosis reported in 2 patients (4%, 1.12 events/100 patient-years).
During the double-blind controlled clinical trials, severe adverse events reported in >1 patient occurring more often in the adalimumab injection-treated patients compared to placebo when adjusted for exposure were deep vein thrombosis reported in 3 patients (0.6%, 1.68 events/100 patient-years), and constipation, leukopenia and fatigue, which were reported in 2 patients (0.4%, 1.12 events/100 patients-years).
The most common adverse event associated with discontinuation reported in >1 subject during induction and maintenance was ulcerative colitis [n=18 (3.8%) and n=8 (3.4%), respectively].
Hidradenitis Suppurativa
Adalimumab injection has been studied in 727 patients with hidradenitis suppurativa in three placebo-controlled studies and one open-label extension study.
Table 11 summarizes adverse drug reactions reported at a rate of at least 1% in hidradenitis suppurativa patients treated with adalimumab injection during the placebo-controlled portion of the studies.
Table 11 Number and Percentage of Patients ≥1% Reporting Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug in Controlled Hidradenitis Suppurativa Studies (Studies M10-467, M11-313 and M11-810)
System Organ Class (SOC) | Adalimumab injection 40 mg Every other week | Adalimumab injection 40 mg Weekly | Placebo | ||||
|---|---|---|---|---|---|---|---|
System Organ Class (SOC) | Adalimumab injection 40 mg Every other week | Adalimumab injection 40 mg Weekly | Placebo | ||||
System Organ Class (SOC) | Adalimumab injection 40 mg Every other week | Adalimumab injection 40 mg Weekly | Placebo | ||||
N=52 n (%) | N=367 n (%) | N=366 n (%) | |||||
N=52 n (%) | N=367 n (%) | N=366 n (%) | |||||
N=52 n (%) | N=367 n (%) | N=366 n (%) | |||||
| Eye Disorders | |||||||
| Cataract | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Conjunctivitis | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Vision blurred | 1 (1.9) | 1 (0.3) | 0 (0.0) | ||||
| Gastrointestinal Disorders | |||||||
| Abdominal pain | 1 (1.9) | 1 (0.3) | 0 (0.0) | ||||
| Abdominal pain upper | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Diarrhoea | 1 (1.9) | 8 (2.2) | 3 (0.8) | ||||
| Nausea | 1 (1.9) | 6 (1.6) | 8 (2.2) | ||||
| Vomiting | 1 (1.9) | 3 (0.8) | 3 (0.8) | ||||
| General Disorders and Administration Site Conditions | |||||||
| Asthenia | 0 (0.0) | 1 (0.3) | 5 (1.4) | ||||
| Chills | 1 (1.9) | 0 (0.0) | 1 (0.3) | ||||
| Fatigue | 1 (1.9) | 4 (1.1) | 4 (1.1) | ||||
| Injection site erythema | 0 (0.0) | 5 (1.4) | 0 (0.0) | ||||
| Injection site pain | 0 (0.0) | 6 (1.6) | 6 (1.6) | ||||
| Injection site pruritus | 0 (0.0) | 5 (1.4) | 0 (0.0) | ||||
| Injection site reaction | 1 (1.9) | 3 (0.8) | 1 (0.3) | ||||
| Oedema | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Pain | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Pyrexia | 1 (1.9) | 1 (0.3) | 1 (0.3) | ||||
| Infections and Infestations | |||||||
| Bronchitis | 0 (0.0) | 2 (0.5) | 5 (1.4) | ||||
| Cellulitis | 0 (0.0) | 0 (0.0) | 4 (1.1) | ||||
| Gastroenteritis | 1 (1.9) | 2 (0.5) | 0 (0.0) | ||||
| Herpes simplex | 2 (3.8) | 0 (0.0) | 1 (0.3) | ||||
| Localised infection | 1 (1.9) | 1 (0.3) | 0 (0.0) | ||||
| Nasopharyngitis | 3 (5.8) | 11 (3.0) | 9 (2.5) | ||||
| Pneumonia | 1 (1.9) | 0 (0.0) | 3 (0.8) | ||||
| Skin bacterial infection | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Tooth abscess | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Upper respiratory tract infection | 3 (5.8) | 7 (1.9) | 6 (1.6) | ||||
| Urinary tract infection | 0 (0.0) | 3 (0.8) | 4 (1.1) | ||||
| Vaginal infection | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Musculoskeletal and Connective Tissue Disorders | |||||||
| Arthralgia | 0 (0.0) | 5 (1.4) | 0 (0.0) | ||||
| Pain in extremity | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Nervous System Disorders | |||||||
| Dizziness | 1 (1.9) | 6 (1.6) | 1 (0.3) | ||||
| Dysgeusia | 1 (1.9) | 2 (0.5) | 0 (0.0) | ||||
| Headache | 4 (7.7) | 17 (4.6) | 11 (3.0) | ||||
| Respiratory, Thoracic and Mediastinal Disorders | |||||||
| Cough | 0 (0.0) | 4 (1.1) | 2 (0.5) | ||||
| Dyspnea | 1 (1.9) | 1 (0.3) | 1 (0.3) | ||||
| Interstitial lung disease | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Nasal congestion | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Oropharyngeal pain | 1 (1.9) | 1 (0.3) | 0 (0.0) | ||||
| Sneezing | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Hidradenitis | 2 (3.8) | 11 (3.0) | 16 (4.4) | ||||
| Pruritus | 2 (3.8) | 2 (0.5) | 1 (0.3) | ||||
| Pruritus generalised | 1 (1.9) | 0 (0.0) | 0 (0.0) | ||||
Psoriasis
Adalimumab injection has been studied in 1,696 patients with psoriasis in placebo-controlled and open-label extension studies. The safety profile for patients with psoriasis treated with adalimumab injection was similar to the safety profile seen in patients with rheumatoid arthritis. Safety results of the long-term open-label study are consistent with the known safety profile of adalimumab injection in other psoriasis studies. Table 12 summarizes adverse drug reactions reported at a rate of at least 1% in psoriasis patients treated with an initial dose of adalimumab injection 80 mg followed by adalimumab injection 40 mg every other week compared to placebo or methotrexate.
Table 12 Number and Percentage of Patients ≥1% Reporting Treatment-Emergent Adverse Events Possibly or Probably Related to Study Drug in Controlled Psoriasis Studies (Studies M03-656, M04-716 and M02-528)
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo + MTX | |
|---|---|---|---|
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo + MTX | |
N=966 n (%) | N=613 n (%) | ||
N=966 n (%) | N=613 n (%) | ||
| Gastrointestinal Disorders | |||
| Nausea | 10 (1.0) | 11 (1.8) | |
| General Disorders and Administration Site Conditions | |||
| Injection site reaction | 29 (3.0) | 9 (1.5) | |
| Injection site irritation | 16 (1.7) | 6 (1.0) | |
| Injection site pain | 14 (1.5) | 9 (1.5) | |
| Fatigue | 10 (1.0) | 5 (0.8) | |
| Infections and Infestations | |||
| Upper respiratory infection | 12 (1.2) | 3 (0.5) | |
| Musculoskeletal and Connective Tissue Disorders | |||
| Arthralgia | 10 (1.0) | 3 (0.5) | |
| Nervous System Disorders | |||
| Headache | 19 (2.0) | 14 (2.3) | |
| Definition(s): s.c.=subcutaneous; eow=every other week; MTX=methotrexate | |||
Uveitis
Adalimumab injection has been studied in 500 patients with uveitis in placebo-controlled studies. The safety profile for patients with uveitis treated with adalimumab injection was consistent with the known safety profile of adalimumab injection. Safety results of the long-term open-label study are generally consistent with the known safety profile of adalimumab injection in the controlled uveitis studies; the exposure-adjusted incidence rates of severe and serious adverse events (including serious infections) were higher in patients who received concomitant systemic corticosteroids and immunosuppressants. Table 13 summarizes adverse drug reactions reported at a rate of at least 1% in uveitis patients treated with an initial dose of adalimumab injection 80 mg followed by adalimumab injection 40 mg every other week compared to placebo.
Table 13 Number and Percentage of Patients ≥1% Reporting Treatment-Emergent Adverse Events Possibly or Probably Related to Study Drug in Controlled Uveitis Studies (Studies M10-877 and M10-880)
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo | |||||
|---|---|---|---|---|---|---|---|
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo | |||||
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo | |||||
| System Organ Class (SOC) | Adalimumab injection 80 mg x 1, then 40 mg s.c. eow | Placebo | |||||
N=250; n (%) | N=250; n (%) | ||||||
N=250; n (%) | N=250; n (%) | ||||||
N=250; n (%) | N=250; n (%) | ||||||
N=250; n (%) | N=250; n (%) | ||||||
| Cardiac Disorders | 6 (2.4) | 1 (0.4) | |||||
| Palpitations | 4 (1.6) | 1 (0.4) | |||||
| Ear and Labyrinth Disorders | 2 (0.8) | 4 (1.6) | |||||
| Tinnitus | 1 (0.4) | 3 (1.2) | |||||
| Endocrine Disorders | 5 (2.0) | 4 (1.6) | |||||
| Cushingoid | 3 (1.2) | 3 (1.2) | |||||
| Eye Disorders | 20 (8.0) | 20 (8.0) | |||||
| Cataract | 3 (1.2) | 4 (1.6) | |||||
| Cataract subcapsular | 3 (1.2) | 1 (0.4) | |||||
| Cystoid Macular Oedema | 3 (1.2) | 1 (0.4) | |||||
| Uveitis | 3 (1.2) | 6 (2.4) | |||||
| Gastrointestinal Disorders | 26 (10.4) | 17 (6.8) | |||||
| Abdominal discomfort | 3 (1.2) | 1 (0.4) | |||||
| Abdominal pain upper | 4 (1.6) | 2 (0.8) | |||||
| Dry mouth | 4 (1.6) | 0 | |||||
| Dyspepsia | 3 (1.2) | 2 (0.8) | |||||
| Nausea | 5 (2.0) | 7 (2.8) | |||||
| General Disorders and Administration Site Conditions | 50 (20.0) | 38 (15.2) | |||||
| Fatigue | 13 (5.2) | 11 (4.4) | |||||
| Injection site bruising | 2 (0.8) | 3 (1.2) | |||||
| Injection site erythema | 4 (1.6) | 1 (0.4) | |||||
| Injection site pain | 10 (4.0) | 12 (4.8) | |||||
| Injection site rash | 6 (2.4) | 1 (0.4) | |||||
| Injection site swelling | 4 (1.6) | 0 | |||||
| Malaise | 2 (0.8) | 4 (1.6) | |||||
| Oedema peripheral | 5 (2.0) | 3 (1.2) | |||||
| Peripheral swelling | 3 (1.2) | 0 | |||||
| Pyrexia | 4 (1.6) | 2 (0.8) | |||||
| Infections and Infestations | 51 (20.4) | 29 (11.6) | |||||
| Bronchitis | 4 (1.6) | 3 (1.2) | |||||
| Influenza | 1 (0.4) | 3 (1.2) | |||||
| Nasopharyngitis | 14 (5.6) | 7 (2.8) | |||||
| Rash pustular | 4 (1.6) | 0 | |||||
| Upper respiratory tract infection | 7 (2.8) | 3 (1.2) | |||||
| Urinary tract infection | 7 (2.8) | 5 (2.0) | |||||
| Investigations | 32 (12.8) | 18 (7.2) | |||||
| Alanine aminotransferase increased | 8 (3.2) | 1 (0.4) | |||||
| Aspartate aminotransferase increased | 7 (2.8) | 0 | |||||
| Blood creatinine increased | 3 (1.2) | 2 (0.8) | |||||
| Blood pressure increased | 4 (1.6) | 0 | |||||
| Intraocular pressure increased | 5 (2.0) | 3 (1.2) | |||||
| Weight increased | 5 (2.0) | 2 (0.8) | |||||
| White blood cell count increased | 3 (1.2) | 1 (0.4) | |||||
| Metabolism and Nutrition Disorders | 12 (4.8) | 8 (3.2) | |||||
| Diabetes mellitus | 0 | 4 (1.6) | |||||
| Increased appetite | 1 (0.4) | 4 (1.6) | |||||
| Musculoskeletal and Connective Tissue Disorders | 39 (15.6) | 30 (12.0) | |||||
| Arthralgia | 14 (5.6) | 12 (4.8) | |||||
| Back pain | 3 (1.2) | 1 (0.4) | |||||
| Joint swelling | 2 (0.8) | 3 (1.2) | |||||
| Muscle spasms | 5 (2.0) | 2 (0.8) | |||||
| Musculoskeletal stiffness | 3 (1.2) | 2 (0.8) | |||||
| Myalgia | 4 (1.6) | 3 (1.2) | |||||
| Pain in extremity | 8 (3.2) | 1 (0.4) | |||||
| Nervous System Disorders | 29 (11.6) | 16 (6.4) | |||||
| Dizziness | 2 (0.8) | 4 (1.6) | |||||
| Headache | 12 (4.8) | 12 (4.8) | |||||
| Paraesthesia | 7 (2.8) | 1 (0.4) | |||||
| Tremor | 4 (1.6) | 1 (0.4) | |||||
| Psychiatric Disorders | 24 (9.6) | 10 (4.0) | |||||
| Anxiety | 4 (1.6) | 0 | |||||
| Insomnia | 13 (5.2) | 7 (2.8) | |||||
| Respiratory, Thoracic and Mediastinal Disorders | 18 (7.2) | 8 (3.2) | |||||
| Cough | 5 (2.0) | 3 (1.2) | |||||
| Dyspnoea | 2 (0.8) | 3 (1.2) | |||||
| Skin and Subcutaneous Tissue Disorders | 40 (16.0) | 36 (14.4) | |||||
| Acne | 5 (2.0) | 7 (2.8) | |||||
| Alopecia | 3 (1.2) | 6 (2.4) | |||||
| Dermatitis allergic | 3 (1.2) | 2 (0.8) | |||||
| Eczema | 3 (1.2) | 1 (0.4) | |||||
| Erythema | 4 (1.6) | 3 (1.2) | |||||
| Hyperhidrosis | 6 (2.4) | 3 (1.2) | |||||
| Pruritus | 5 (2.0) | 1 (0.4) | |||||
| Rash | 3 (1.2) | 4 (1.6) | |||||
| Vascular Disorders | 12 (4.8) | 10 (4.0) | |||||
| Hot flush | 4 (1.6) | 2 (0.8) | |||||
| Hypertension | 4 (1.6) | 3 (1.2) | |||||
| Definition(s): s.c.=subcutaneous; eow=every other week | |||||||
During the double-masked controlled clinical trials, the most common (≥5%) adverse drug reactions in subjects receiving adalimumab injection were nasopharyngitis (n=44, 17.6%), arthralgia (n=38, 15.2%), headache (n=30, 12.0%), fatigue (n=26, 10.4%), urinary tract infection (n=21, 8.4%), uveitis (n=20, 8.0%), back pain (n=19, 7.6%), insomnia (n=18, 7.2%), cough (n=18, 7.2%), eye pain (n=18, 7.2%), and upper respiratory tract infection (n=15, 6.0%).
During the double-masked controlled clinical trials, the most common serious adverse event occurring in >1 patient more often in the adalimumab injection-treated patients compared to placebo was pneumonia (n=2). During the overall adalimumab injection uveitis development program, including the double-masked controlled, and open-label extension trials, the most frequently reported serious adverse event was cataract (n=7 patients).
During the double-masked controlled clinical trials, severe adverse events reported in >1 patient occurring more often in the adalimumab injection-treated patients compared to placebo were diarrhea (n=2) and pneumonia (n=2). During the overall adalimumab injection uveitis development program, including the double-masked controlled, and open-label extension trials, the most common severe adverse events reported were hypertension (n=5 patients), pneumonia, urinary tract infection, reduced visual acuity and severe vision loss (n=4 patients each).
Other Common Clinical Trial Adverse Drug Reactions
Other clinical trial adverse reactions occurring at an incidence of ≥1% that were observed among the various indications include:
Eye Disorders:
conjunctivitis, visual impairment
Renal and Urinary Disorders:
hematuria, renal impairment
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
Polyarticular Juvenile Idiopathic Arthritis
Table 14 Number and Percentage of Subjects with ≥1% Reporting Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug During the Double Blind Placebo-Controlled Phase in the Polyarticular JIA Trial (Study DE038)
System Organ Class MedDRA 12.1 Preferred Term | MTX | Non-MTX | Overall | |||||||||||||||||||||||
System Organ Class MedDRA 12.1 Preferred Term | MTX | Non-MTX | Overall | |||||||||||||||||||||||
System Organ Class MedDRA 12.1 Preferred Term | MTX | Non-MTX | Overall | |||||||||||||||||||||||
System Organ Class MedDRA 12.1 Preferred Term | MTX | Non-MTX | Overall | |||||||||||||||||||||||
| Placebo | Adalimumab injection | Placebo | Adalimumab injection | Placebo | Adalimumab injection | |||||||||||||||||||||
| Placebo | Adalimumab injection | Placebo | Adalimumab injection | Placebo | Adalimumab injection | |||||||||||||||||||||
| Placebo | Adalimumab injection | Placebo | Adalimumab injection | Placebo | Adalimumab injection | |||||||||||||||||||||
| Placebo | Adalimumab injection | Placebo | Adalimumab injection | Placebo | Adalimumab injection | |||||||||||||||||||||
N=37 n (%) | N=38 n (%) | N=28 n (%) | N=30 n (%) | N=65 n (%) | N=68 n (%) | |||||||||||||||||||||
N=37 n (%) | N=38 n (%) | N=28 n (%) | N=30 n (%) | N=65 n (%) | N=68 n (%) | |||||||||||||||||||||
N=37 n (%) | N=38 n (%) | N=28 n (%) | N=30 n (%) | N=65 n (%) | N=68 n (%) | |||||||||||||||||||||
N=37 n (%) | N=38 n (%) | N=28 n (%) | N=30 n (%) | N=65 n (%) | N=68 n (%) | |||||||||||||||||||||
| Any at least possibly related adverse event | 17 (45.9) | 22 (57.9) | 9 (32.1) | 16 (53.3) | 26 (40.0) | 38 (55.9) | ||||||||||||||||||||
| Blood and Lymphatic System Disorders | 0 | 2 (5.3) | 0 | 1 (3.3) | 0 | 3 (4.4) | ||||||||||||||||||||
| Leukopenia | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Neutropenia | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Ear and Labyrinth Disorders | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Ear pain | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Gastrointestinal Disorders | 1 (2.7) | 1 (2.6) | 0 | 0 | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Gastroduodenitis | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Vomiting | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| General Disorders and Administration Site Conditions | 10 (27.0) | 15 (39.5) | 6 (21.4) | 11 (36.7) | 16 (24.6) | 26 (38.2) | ||||||||||||||||||||
| Application site reaction | 1 (2.7) | 1 (2.6) | 0 | 0 | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Fatigue | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Influenza like illness | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Injection site erythema | 1 (2.7) | 2 (5.3) | 0 | 1 (3.3) | 1 (1.5) | 3 (4.4) | ||||||||||||||||||||
| Injection site haematoma | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Injection site hypersensitivity | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Injection site pain | 7 (18.9) | 7 (18.4) | 3 (10.7) | 9 (30.0) | 10 (15.4) | 16 (23.5) | ||||||||||||||||||||
| Injection site pruritus | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Injection site reaction | 1 (2.7) | 7 (18.4) | 1 (3.6) | 3 (10.0) | 2 (3.1) | 10 (14.7) | ||||||||||||||||||||
| Pain | 0 | 1 (2.6) | 2 (7.1) | 2 (6.7) | 2 (3.1) | 3 (4.4) | ||||||||||||||||||||
| Pyrexia | 0 | 2 (5.3) | 0 | 0 | 0 | 2 (2.9) | ||||||||||||||||||||
| Immune System Disorder | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Hypersensitivity | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Infections and Infestations | 7 (18.9) | 10 (26.3) | 3 (10.7) | 6 (20.0) | 10 (15.4) | 16 (23.5) | ||||||||||||||||||||
| Acute tonsillitis | 1 (2.7) | 1 (2.6) | 0 | 0 | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Bronchitis | 1 (2.7) | 0 | 0 | 1 (3.3) | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Ear infection | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Folliculitis | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Fungal infection | 0 | 0 | 1 (3.6) | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Herpes simplex | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Herpes virus infection | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Impetigo | 0 | 1 (2.6) | 0 | 1 (3.3) | 0 | 2 (2.9) | ||||||||||||||||||||
| Influenza | 0 | 1 (2.6) | 1 (3.6) | 1 (3.3) | 1 (1.5) | 2 (2.9) | ||||||||||||||||||||
| Molluscum contagiosum | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Oral herpes | 1 (2.7) | 1 (2.6) | 0 | 0 | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Paronychia | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Pharyngotonsillitis | 1 (2.7) | 0 | 0 | 1 (3.3) | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Rhinitis | 0 | 2 (5.3) | 0 | 1 (3.3) | 0 | 3 (4.4) | ||||||||||||||||||||
| Sinusitis | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Staphylococcal skin infection | 0 | 0 | 1 (3.6) | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Upper respiratory tract infection | 2 (5.4) | 3 (7.9) | 0 | 2 (6.7) | 2 (3.1) | 5 (7.4) | ||||||||||||||||||||
| Urinary tract infection | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Viral infection | 1 (2.7) | 3 (7.9) | 0 | 0 | 1 (1.5) | 3 (4.4) | ||||||||||||||||||||
| Viral upper respiratory tract infection | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | |||||||||||||||||||||
| Injury, Poisoning and Procedural Complications | 1 (2.7) * | 0* | 1 (3.6) * | 0* | 2 (3.1) * | 0* | ||||||||||||||||||||
| Excoriation† | 1 (2.7) | 4 (10.5) | 1 (3.6) | 3 (10.0) | 2 (3.1) | 7 (10.3) | ||||||||||||||||||||
| Injury | 0 | 0 | 1 (3.6) | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Scratch | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Investigations | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Lymphocyte count increased | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Neutrophil count decreased | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Metabolism and Nutrition Disorders | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Enzyme abnormality | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Musculoskeletal and Connective Tissue Disorders | 3 (8.1) | 1 (2.6) | 0 | 1 (3.3) | 3 (4.6) | 2 (2.9) | ||||||||||||||||||||
| Arthralgia | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Groin pain | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Juvenile arthritis | 1 (2.7) | 1 (2.6) | 0 | 0 | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Rheumatoid arthritis | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Nervous System Disorders | 1 (2.7) | 0 | 0 | 1 (3.3) | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Headache | 1 (2.7) | 0 | 0 | 1 (3.3) | 1 (1.5) | 1 (1.5) | ||||||||||||||||||||
| Renal and Urinary Disorders | 0 | 0 | 2 (7.1) | 0 | 2 (3.1) | 0 | ||||||||||||||||||||
| Dysuria | 0 | 0 | 1 (3.6) | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Proteinuria | 0 | 0 | 1 (3.6) | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Respiratory, Thoracic and Mediastinal Disorders | 0 | 2 (5.3) | 0 | 1 (3.3) | 0 | 3 (4.4) | ||||||||||||||||||||
| Asthma | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Cough | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Epistaxis | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
| Skin and Subcutaneous Tissue Disorders | 1 (2.7) * | 1 (2.6) * | 0 | 1 (3.3) * | 1 (1.5) * | 2 (2.9) * | ||||||||||||||||||||
| Acne | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Dermatitis | 1 (2.7) | 0 | 0 | 0 | 1 (1.5) | 0 | ||||||||||||||||||||
| Rash† | 0 | 1 (2.6) | 0 | 2 (6.7) | 0 | 3 (4.4) | ||||||||||||||||||||
| Rash papular | 0 | 0 | 0 | 1 (3.3) | 0 | 1 (1.5) | ||||||||||||||||||||
| Skin lesion | 0 | 1 (2.6) | 0 | 0 | 0 | 1 (1.5) | ||||||||||||||||||||
* Total only includes values for the terms that were considered possibly or probably related by the investigator. † Term was not considered possibly or probably related as assessed by the investigator; however, these terms were considered more common in patients treated with adalimumab injection vs. placebo in the clinical trial. | ||||||||||||||||||||||||||
In Study DE038, adalimumab injection was studied in 171 patients aged 4 to 17 years with polyarticular JIA. Serious adverse events were observed in 28% of patients treated with adalimumab injection and included neutropenia, streptococcal pharyngitis, increased aminotransferases, herpes zoster, myositis, metrorrhagia and appendicitis. Serious infections were observed in 6.4% of patients treated with adalimumab injection and included cases of herpes zoster, appendicitis, pneumonia, urinary tract infection, streptococcal pharyngitis, viral infection and cervicitis. A total of 45% of patients experienced an infection while receiving adalimumab injection with or without concomitant methotrexate in the first 16 weeks of treatment (see 7 WARNINGS AND PRECAUTIONS, Infections). Granuloma annulare was reported in two patients (see 7 WARNINGS AND PRECAUTIONS, Malignancies).
During the double-blind phase of Study DE038, the most common (≥5%) adverse reactions occurring in the JIA population treated with adalimumab injection were viral infection (18%), injection site pain (18%), upper respiratory tract infection (16%), injection site reaction (15%), contusion (13%), excoriation (10%), rhinitis (7%), vomiting (6%) and drug hypersensitivity (6%).
Throughout Study DE038, 6% of patients had mild to moderate allergic reaction adverse events primarily localized allergic hypersensitivity reactions and urticaria (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions).
In the JIA trial, 10% of patients treated with adalimumab injection who were negative at baseline for anti-double-stranded DNA antibodies developed positive titers after 48 weeks of treatment (see 8.1 Adverse Reaction Overview, Immunogenicity, Pediatric).
In Study M10-444, adalimumab injection was studied in 32 patients who were 2 to <4 years of age or 4 years of age and older weighing <15 kg with polyarticular JIA. The safety profile for this patient population was similar to the safety profile seen in Study DE038.
In Study M10-444, 78% of patients experienced an infection while receiving adalimumab injection. These included nasopharyngitis, bronchitis, upper respiratory tract infection, otitis media, and were mostly mild to moderate in severity. Serious infections were observed in 9% of patients receiving adalimumab injection in the study and included dental caries, rotavirus gastroenteritis, and varicella.
In Study M10-444, non-serious allergic reactions were observed in 6% of patients and included intermittent urticaria and rash, which were all mild in severity.
Hidradenitis Suppurativa
There are no clinical trials conducted to evaluate the safety of adalimumab injection in adolescents with hidradenitis suppurativa (HS).
Pediatric Uveitis
Table 15 summarizes adverse drug reactions reported in the SYCAMORE study at a rate of at least 1% in the indicated pediatric patient population with active JIA-associated chronic noninfectious anterior uveitis treated with adalimumab injection in combination with methotrexate.
Table 15 Number and Percentage of Patients with ≥1% Treatment-Emergent Adverse Events at Least Possibly Related to Study Drug in the SYCAMORE Pediatric Uveitis Study
| System Organ Class (SOC) | Adalimumab injection N=60 n (%) | Placebo N=30 n (%) |
|---|---|---|
| System Organ Class (SOC) | Adalimumab injection N=60 n (%) | Placebo N=30 n (%) |
| System Organ Class (SOC) | Adalimumab injection N=60 n (%) | Placebo N=30 n (%) |
| System Organ Class (SOC) | Adalimumab injection N=60 n (%) | Placebo N=30 n (%) |
| Blood and Lymphatic System Disorders | 4 (6.7) | 0 |
| Lymphadenopathy | 3 (5.0) | 0 |
| Neutropenia | 1 (1.7) | 0 |
| Eye Disorders | 4 (6.7) | 4 (13.3) |
| Anterior chamber flare | 0 | 1 (3.3) |
| Dry eye | 1 (1.7) | 0 |
| Eye inflammation | 1 (1.7) | 0 |
| Eye pain | 1 (1.7) | 0 |
| Uveitis | 0 | 3 (10.0) |
| Visual impairment | 1 (1.7) | 0 |
| Gastrointestinal Disorders | 10 (16.7) | 2 (6.7) |
| Abdominal pain | 1 (1.7) | 0 |
| Diarrhoea | 4 (6.7) | 0 |
| Food poisoning | 1 (1.7) | 0 |
| Nausea | 2 (3.3) | 0 |
| Vomiting | 7 (11.7) | 2 (6.7) |
| General Disorders and Administration Site Conditions | 23 (38.3) | 5 (16.7) |
| Chest discomfort | 1 (1.7) | 0 |
| Fatigue | 0 | 1 (3.3) |
| Influenza like illness | 1 (1.7) | 0 |
| Injection site erythema | 3 (5.0) | 1 (3.3) |
| Injection site mass | 2 (3.3) | 0 |
| Injection site pain | 5 (8.3) | 2 (6.7) |
| Injection site pruritus | 3 (5.0) | 0 |
| Injection site reaction | 6 (10.0) | 0 |
| Injection site swelling | 3 (5.0) | 1 (3.3) |
| Injection site vesicles | 1 (1.7) | 0 |
| Malaise | 1 (1.7) | 0 |
| Pyrexia | 8 (13.3) | 1 (3.3) |
| Swelling | 1 (1.7) | 0 |
| Infections and Infestations | 32 (53.3) | 8 (26.7) |
| Candida infection | 1 (1.7) | 0 |
| Cellulitis | 1 (1.7) | 0 |
| Conjunctivitis viral | 1 (1.7) | 0 |
| Ear infection | 3 (5.0) | 2 (6.7) |
| Eye infection | 1 (1.7) | 0 |
| Herpes simplex | 1 (1.7) | 0 |
| Herpes zoster | 0 | 1 (3.3) |
| Impetigo | 3 (5.0) | 1 (3.3) |
| Infected bites | 1 (1.7) | 0 |
| Infection | 1 (1.7) | 0 |
| Localised infection | 0 | 1 (3.3) |
| Lower respiratory tract infection | 8 (13.3) | 2 (6.7) |
| Molluscum contagiosum | 2 (3.3) | 0 |
| Nasopharyngitis | 6 (10.0) | 2 (6.7) |
| Oral herpes | 2 (3.3) | 1 (3.3) |
| Paronychia | 2 (3.3) | 1 (3.3) |
| Pharyngitis | 2 (3.3) | 0 |
| Pneumonia | 1 (1.7) | 0 |
| Rhinitis | 1 (1.7) | 0 |
| Scarlet fever | 1 (1.7) | 0 |
| Skin infection | 2 (3.3) | 0 |
| Staphylococcal infection | 1 (1.7) | 0 |
| Streptococcal infection | 1 (1.7) | 0 |
| Tonsillitis | 10 (16.7) | 0 |
| Upper respiratory tract infection | 3 (5.0) | 1 (3.3) |
| Urethritis | 0 | 1 (3.3) |
| Urinary tract infection | 6 (10.0) | 2 (6.7) |
| Varicella | 1 (1.7) | 0 |
| Viral infection | 8 (13.3) | 1 (3.3) |
| Injury, Poisoning and Procedural Complications | 1 (1.7) | 0 |
| Contusion | 1 (1.7) | 0 |
| Investigations | 6 (10.0) | 1 (3.3) |
| Alanine aminotransferase increased | 3 (5.0) | 0 |
| Aspartate aminotransferase increased | 2 (3.3) | 0 |
| Blood alkaline phosphatase increased | 1 (1.7) | 0 |
| Liver function test abnormal | 1 (1.7) | 0 |
| Neutrophil count decreased | 0 | 1 (3.3) |
| Red blood cell sedimentation rate abnormal | 1 (1.7) | 0 |
| Rubulavirus test positive | 1 (1.7) | 0 |
| Metabolism and Nutrition Disorders | 3 (5.0) | 0 |
| Decreased appetite | 2 (3.3) | 0 |
| Dehydration | 1 (1.7) | 0 |
| Musculoskeletal and Connective Tissue Disorders | 5 (8.3) | 1 (3.3) |
| Arthralgia | 3 (5.0) | 1 (3.3) |
| Arthritis | 1 (1.7) | 0 |
| Joint stiffness | 1 (1.7) | 0 |
| Pain in extremity | 1 (1.7) | 0 |
| Neoplasms Benign, Malignant and Unspecified (including cysts and polyps) | 4 (6.7) | 0 |
| Skin papilloma | 4 (6.7) | 0 |
| Nervous System Disorders | 5 (8.3) | 1 (3.3) |
| Headache | 5 (8.3) | 1 (3.3) |
| Reproductive System and Breast Disorders | 1 (1.7) | 0 |
| Pruritus genital | 1 (1.7) | 0 |
| Respiratory, Thoracic and Mediastinal Disorders | 12 (20.0) | 2 (6.7) |
| Cough | 9 (15.0) | 2 (6.7) |
| Nasal discomfort | 2 (3.3) | 0 |
| Oropharyngeal pain | 8 (13.3) | 0 |
| Productive cough | 1 (1.7) | 0 |
| Snoring | 1 (1.7) | 0 |
| Tonsillar hypertrophy | 1 (1.7) | 0 |
| Skin and Subcutaneous Tissue Disorders | 3 (5.0) | 2 (6.7) |
| Dermatitis | 0 | 1 (3.3) |
| Erythema | 1 (1.7) | 0 |
| Ingrowing nail | 1 (1.7) | 0 |
| Rash | 1 (1.7) | 1 (3.3) |
In the SYCAMORE study, adalimumab injection was studied in 90 pediatric patients (randomized 2:1 to adalimumab: placebo) with active JIA-associated chronic non-infectious anterior uveitis. Overall, serious adverse events were observed in 22% of patients treated with adalimumab injection in combination with methotrexate and included varicella, streptococcal infections, viral infection, diarrhea, syncope, scarlet fever, cellulitis, infected bites, lower respiratory tract infection, cataract, testes exploration, antiviral prophylaxis, food poisoning, and tonsillar hypertrophy. Serious infections were observed in 13% of patients with adalimumab injection. Serious adverse events were more frequent in children 4 years of age and younger.
8.3 Less Common Clinical Trial Adverse Reactions
Infrequent serious adverse drug reactions occurring at an incidence of less than 1% in patients treated with adalimumab injection in RA Studies DE009, DE011, DE019, DE031 and DE013, JIA Study DE038, PsA Studies M02-518 and M02-570, AS Studies M03-607 and M03-606, CD Maintenance Studies M02-404 and M02-433, UC Studies M06-826 and M06-827, HS Studies M10-467, M11-313 and M11-810, Ps Studies M03-656, M04-716, and M02-528, and adult uveitis Studies M10-877 and M10-880:
Blood and Lymphatic System Disorders:
agranulocytosis, anemia, eosinophilia, leukopenia, lymphadenopathy, lymphocytosis, neutropenia, pancytopenia
Cardiac Disorders:
arrhythmia supraventricular, cardiac arrest, chest pain, palpitations
Eye Disorders:
blepharitis, diplopia, eye swelling
Gastrointestinal Disorders:
abdominal pain, anal fistula, Crohn’s disease, frequent bowel movements, hematochezia, hemorrhoidal hemorrhage, pancreatitis, rectal hemorrhage, small intestine obstruction
General Disorders and Administration Site Conditions:
death, non-cardiac chest pain, pyrexia
Hepatobiliary Disorders:
hepatic necrosis
Immune System Disorders:
hypersensitivity
Infections and Infestations:
abscess, abscess limb, arthritis bacterial, bronchitis, bronchopneumonia, cellulitis, cystitis, device-related infection, diverticulitis, erysipelas, escherichia sepsis, gastroenteritis, genital herpes, herpes virus infection, herpes zoster, histoplasmosis, infected skin ulcer, infection, lobar pneumonia, lower respiratory tract infection, meningitis viral, mycobacterium avium complex infection, necrotizing fasciitis, perianal abscess, pharyngitis, pneumonia, pneumonia pneumococcal, pyelonephritis, respiratory tract infection, sepsis, septic shock, sinusitis, tuberculosis, urinary tract infection, urosepsis, viral infection, wound infection
Injury, Poisoning and Procedural Complications:
postoperative wound complication
Investigations:
double-stranded DNA antibody, hepatic enzyme increased
Metabolism and Nutrition Disorders:
hyperglycemia*
Musculoskeletal and Connective Tissue Disorders:
arthritis, arthropathy, back pain, muscular weakness, musculoskeletal chest pain, osteitis, rheumatoid arthritis, systemic lupus erythematosus
Neoplasms Benign, Malignant and Unspecified (Including Cysts and Polyps):
basal cell carcinoma, B-cell lymphoma, breast cancer, malignant melanoma in situ, metastases to liver, ovarian cancer, squamous cell carcinoma, testicular seminoma (pure)
Nervous System Disorders:
clonus, hyperreflexia, hydrocephalus, hypertensive encephalopathy, intention tremor, multiple sclerosis, paresthesia, tremor, neuropathy
Pregnancy, Puerperium and Perinatal Conditions:
abortion spontaneous
Psychiatric Disorders:
confusional state
Renal and Urinary Disorders:
nocturia
Reproductive System and Breast Disorders:
cervical dysplasia, endometrial hyperplasia
Respiratory, Thoracic and Mediastinal Disorders:
bronchospasm, lung infiltration, pleural effusion, pleurisy, pneumonitis, respiratory failure
Skin and Subcutaneous Tissue Disorders:
psoriasis, pustular psoriasis, rash
Surgical and Medical Procedures:
arthrodesis
Vascular Disorders:
circulatory collapse, rheumatoid vasculitis
*Hyperglycemia ADR in trials were nonserious
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
See 8.2.1 Clinical Trial Adverse Reactions – Pediatrics.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
There are no known laboratory tests that may be helpful in following the patient’s response or in identifying possible adverse reactions.
Adults
In controlled rheumatoid arthritis clinical trials (Studies DE009, DE011, DE019, and DE031), elevations of alanine aminotransferase (ALT) were similar in patients receiving adalimumab injection or placebo. In patients with early rheumatoid arthritis (disease duration of less than three years) (Study DE013), elevations of ALT were more common in the combination arm (adalimumab injection + methotrexate) compared to the methotrexate monotherapy arm or the adalimumab injection monotherapy arm.
In psoriatic arthritis clinical trials, elevations in ALT were more common in psoriatic arthritis patients compared with patients in rheumatoid arthritis clinical studies.
In controlled Crohn’s disease clinical trials and ulcerative colitis, elevations of ALT were similar in patients receiving adalimumab injection or placebo.
In all indications, patients with raised ALT were asymptomatic and in most cases, elevations were transient and resolved on continued treatment.
Pediatrics
In the polyarticular juvenile idiopathic arthritis trial (Study DE038), 10/171 (5.8%) and 5/171 (2.9%) of patients treated with adalimumab injection developed severe elevations of ALT and aspartate aminotransferase (AST) (exceeding >3 times the upper limit of normal [ULN] of ALT and AST, respectively). Forty-two (42)/171 (25%) developed elevations of creatine phosphokinase (CPK); with 10/171 (5.8%) patients with severe elevations.
Liver enzyme elevations were more frequent among those treated with the combination of adalimumab injection and methotrexate than treated with adalimumab injection alone (ALT: 9.5% vs. 2.3%; AST: 5.9% vs. 0%). No ALT or AST elevations ≥3 x ULN occurred in the open-label study of adalimumab injection in patients with polyarticular JIA who were 2 to <4 years of age (Study M10-444).
8.5 Post-Market Adverse Reactions
The following post-market adverse drug reactions have been reported:
Cardiac Disorders:
myocardial infarction
Gastrointestinal Disorders:
diverticulitis, intestinal perforation, pancreatitis
General disorders and administration site conditions:
pyrexia
Hematologic Events:
thrombocytopenia†
Hepatobiliary Disorders:
liver failure, hepatitis, autoimmune hepatitis
Hypersensitivity Reactions:
anaphylaxis†, angioedema, angioneurotic edema
Immune System Disorders:
sarcoidosis
Infections:
infections in infants exposed in utero, legionellosis, listeriosis, reactivation of hepatitis B virus (HBV)†
Musculoskeletal and Connective Tissue Disorders:
lupus-like syndrome† *
Neoplasia:
hepatosplenic T-cell lymphoma (HSTCL)†, leukemia†, Merkel cell carcinoma (neuroendocrine carcinoma of the skin)
Nervous System Disorders:
cerebrovascular accident, demyelinating disorders (e.g., Guillain-Barré syndrome, optic neuritis)
Skin Reactions:
alopecia, cutaneous vasculitis, erythema multiforme, lichenoid skin reaction**, new onset or worsening of psoriasis (including palmoplantar pustular psoriasis) *, Stevens-Johnson syndrome
Respiratory, Thoracic and Mediastinal Disorders:
interstitial lung disease (including pulmonary fibrosis), pulmonary embolism
Vascular Disorders
deep vein thrombosis, systemic vasculitis
† See 7 WARNINGS AND PRECAUTIONS
* See 8.1 Adverse Reaction Overview
** occurring in patients receiving a TNF-antagonist including adalimumab injection
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions
- Serious infections and sepsis, including fatalities, have been reported with the use of TNF-blocking agents, including adalimumab. Many of the serious infections have occurred in patients on concomitant immunosuppressive therapy that, in addition to their rheumatoid arthritis, could predispose them to infections. Tuberculosis and invasive opportunistic fungal infections have been observed in patients treated with TNF-blocking agents, including adalimumab.
9.2 Drug Interactions Overview
Population pharmacokinetic analyses with data from over 1,200 rheumatoid arthritis patients revealed that co-administration of methotrexate had an intrinsic effect on the apparent clearance of adalimumab (CL/F). See 9.4 Drug-Drug Interactions. As expected, there was a trend toward higher apparent clearance of adalimumab with increasing body weight and in the presence of anti-adalimumab antibodies.
Other more minor factors were also identified: higher apparent clearance was predicted in rheumatoid arthritis patients receiving doses lower than the recommended dose, and in rheumatoid arthritis patients with high rheumatoid factor or C-reactive protein (CRP) concentrations. These factors are not likely to be clinically important.
Adalimumab has been studied in rheumatoid arthritis patients taking concomitant methotrexate. See 14.5 Clinical Trials – Reference Biologic Drug. The data do not suggest the need for dose adjustment of either adalimumab or methotrexate.
9.3 Drug-Behavioural Interactions
Adalimumab may have a minor influence on the ability to drive and use machines. Dizziness (including vertigo, vision disorder and fatigue) may occur following administration of adalimumab.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 16 Established or Potential Drug-Drug Interactions
| Concomitant Drug Name | Clinical Comment |
|---|---|
| Concomitant Drug Name | Clinical Comment |
| Abatacept | Concurrent administration of TNF-blockers and abatacept has been associated with an increased risk of infections including serious infections compared to TNF-blockers alone. This combination has not demonstrated |
| increased clinical benefit. Thus, the combined use of TNF-blockers and abatacept is not recommended. | |
| Anakinra | Concurrent administration of anakinra (an interleukin-1 antagonist) and another TNF-blocking agent has been associated with an increased risk of serious infections, an increased risk of neutropenia and no additional benefit compared to these medicinal products alone. Therefore, the combination of anakinra with other TNF-blocking agents, including adalimumab, may also result in similar toxicities. See 7 WARNINGS AND PRECAUTIONS, General, Concurrent Administration of Biologic DMARDS or TNF-antagonists. |
Cytochrome P450 (CYP450) Substrates | The formation of CYP450 enzymes may be suppressed by increased levels of cytokines (e.g., TNFα, IL-6) during chronic inflammation. It is possible for a molecule that antagonizes cytokine activity, such as adalimumab, to influence the formation of CYP450 enzymes. Upon initiation or discontinuation of adalimumab in patients being treated with CYP450 substrates with a narrow therapeutic index, monitoring of the effect (e.g., warfarin) or drug concentration (e.g., cyclosporine or theophylline) is recommended and the individual dose of the drug product may be adjusted as needed. |
| Methotrexate (MTX) | When adalimumab was administered to 21 rheumatoid arthritis patients on stable methotrexate therapy, there were no statistically significant changes in the serum methotrexate concentration profiles. In contrast, after single and multiple dosing, methotrexate reduced adalimumab apparent clearances by 29 and 44% respectively, in patients with rheumatoid arthritis. See 14.5 Clinical Trials – Reference Biologic Drug. |
| Other | Interactions between adalimumab and drugs other than methotrexate have not been evaluated in formal pharmacokinetic studies. In rheumatoid arthritis clinical trials where adalimumab was co-administered with commonly used DMARDs (sulfasalazine, hydrochloroquine, leflunomide and parenteral gold), glucocorticoids, salicylates, nonsteroidal anti-inflammatory drugs or analgesics, no safety signals were seen. There is no data on other DMARDs, and patients with prior treatment with alkylating agents (e.g., cyclophosphamide) were excluded. |
| Definition(s): | DMARDs=disease-modifying anti-rheumatic drugs; MTX=methotrexate; TNF=tumor necrosis factor |
9.5 Drug-Food Interactions
Adalimumab injection is administered as a subcutaneous injection. Interactions with food are therefore not applicable.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
There are no known laboratory tests that may be helpful in following the patient’s response or in identifying possible adverse reactions.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Adalimumab is a recombinant human immunoglobulin (IgG1) monoclonal antibody. Adalimumab has fully human heavy and light chain variable regions, which confer specificity to human tumor necrosis factor (TNF), and human IgG1 heavy chain and kappa light chain sequences. Adalimumab injection binds with high affinity and specificity to soluble tumor necrosis factor (TNF-alpha) but not lymphotoxin (TNF-beta). Idacio (adalimumab injection) is produced by recombinant DNA technology in a mammalian cell expression system. It consists of 1,330 amino acids and has a molecular weight of approximately 148 kilodaltons.
Adalimumab binds specifically to TNF-alpha and blocks its interaction with the p55 and p75 cell surface TNF receptors. Adalimumab also lyses surface TNF-expressing cells in vitro in the presence of complement. Adalimumab does not bind or inactivate TNF-beta. TNF is a naturally occurring cytokine that is involved in normal inflammatory and immune responses. Elevated levels of TNF are found in the synovial fluid of rheumatoid arthritis, including polyarticular JIA, psoriatic arthritis and ankylosing spondylitis patients and play an important role in both pathologic inflammation and joint destruction that are hallmarks of these diseases. Increased levels of TNF are also found in psoriasis plaques, which contribute to the inflammatory response, to the proliferation and decreased maturation of keratinocytes and to the associated vascular damages that are characteristic of the disease. Increased levels of TNF are also found in hidradenitis suppurativa lesions.
Adalimumab also modulates biological responses that are induced or regulated by TNF, including changes in the levels of adhesion molecules responsible for leukocyte migration [ELAM-1, VCAM-1, and ICAM-1 with a half maximal inhibitory concentration (IC50) of 1 to 2 x 10⁻¹⁰M].
10.2 Pharmacodynamics
After treatment with adalimumab, a rapid decrease in levels of acute phase reactants of inflammation [C-reactive protein (CRP) and erythrocyte sedimentation rate (ESR)] and serum cytokines (IL-6) was observed compared to baseline in patients with rheumatoid arthritis. A rapid decrease in CRP levels was also observed in patients with Crohn’s disease, ulcerative colitis, and hidradenitis suppurativa. Serum levels of matrix metalloproteinases (MMP-1 and MMP-3) that produce tissue remodeling responsible for cartilage destruction were also decreased after adalimumab administration.
The serum adalimumab concentration-efficacy relationship as measured by the American College of Rheumatology response criteria (ACR 20) appears to follow the Hill Emax equation as shown in Figure 1.
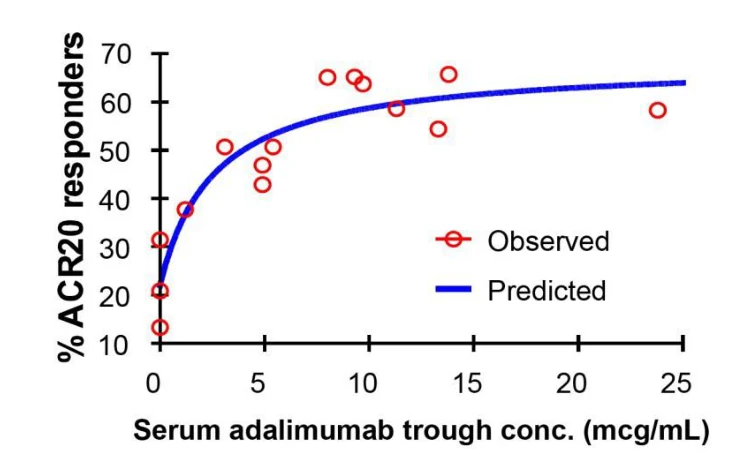
Figure 1. Serum Adalimumab Concentration-Efficacy Relationship as Measured by the American College of Rheumatology Response Criteria (ACR 20)
The half maximal effective concentration (EC50) estimates ranging from 0.8 to 1.4 mcg/mL were obtained through pharmacokinetic/pharmacodynamic modelling of swollen joint count, tender joint count and ACR 20 response from patients participating in Phase 2 and 3 trials.
10.3 Pharmacokinetics
Pediatrics
Following the administration of 24 mg/m2 (up to a maximum of 40 mg) subcutaneously every other week to patients with polyarticular JIA who were 4 to 17 years, the mean trough steady-state (values measured from Week 20 to 48) serum adalimumab concentration was 5.5 ± 5.6 mcg/mL (102% CV) adalimumab monotherapy and 10.9 ± 5.2 mcg/mL (47.7% CV) with concomitant methotrexate. In patients with polyarticular JIA who were 2 to <4 years old or aged 4 and above weighing <15 kg dosed with adalimumab 24 mg/m2, the mean trough steady-state serum adalimumab concentrations was 6.0 ± 6.1 mcg/mL (101% CV) adalimumab monotherapy and 7.9 ± 5.6 mcg/mL (71.2% CV) with concomitant methotrexate.
Adalimumab injection exposure in adolescent hidradenitis suppurativa (HS) patients was predicted using population pharmacokinetic modeling and simulation based on cross indication pharmacokinetics in other pediatric patients (pediatric psoriasis, juvenile idiopathic arthritis, pediatric Crohn’s disease, and enthesitis-related arthritis). Serum adalimumab concentrations in adolescent patients with HS receiving the recommended dosage regimen are predicted to be similar to those observed in adult subjects with HS (steady-state trough concentration of approximately 8 to 10 mcg/mL).
Adalimumab injection exposure in pediatric uveitis patients was predicted using population pharmacokinetic modelling and simulation based on cross-indication pharmacokinetics in other pediatric patients (N=524) (pediatric psoriasis [age 5 to 18 years, n=109], juvenile idiopathic arthritis [age 2 to 17 years, n=181], pediatric Crohn’s disease [age 6 to 17 years, n=189], and enthesitis-related arthritis [age 6 to 18 years, n=45]). No clinical exposure data are available on the use of a loading dose in children <6 years. The predicted exposures indicate that in the absence of methotrexate, a loading dose may lead to an initial increase in systemic exposure.
Adults
The single-dose pharmacokinetics of adalimumab in rheumatoid arthritis patients were determined in several studies with intravenous doses ranging from 0.25 to 10.0 mg/kg. The distribution volume (Vss) ranged from 4.7 to 6.0 L. The systemic clearance of adalimumab is approximately 12 mL/h. The mean terminal half-life was approximately two weeks, ranging from 10 to 20 days across studies. The pharmacokinetics of adalimumab were linear over the dose range of 0.5 to 10.0 mg/kg following a single intravenous dose.
Adalimumab injection mean steady-state trough concentrations of approximately 5 mcg/mL and 8 to 9 mcg/mL, were observed in rheumatoid arthritis patients with and without methotrexate, respectively. The serum adalimumab trough levels at steady-state increased approximately proportionally with dose following 20, 40 and 80 mg every other week and every week subcutaneous dosing. In long-term studies with dosing more than two years, there was no evidence of changes in clearance over time.
Population pharmacokinetic analyses in patients with rheumatoid arthritis revealed that there was a trend toward higher apparent clearance of adalimumab in the presence of anti-adalimumab antibodies.
In patients with psoriatic arthritis, adalimumab mean steady-state trough concentrations of 8.5 to 12 mcg/mL and 6 to 10 mcg/mL were observed in patients with and without methotrexate, respectively.
In patients with Crohn’s disease, the loading dose of 160 mg adalimumab on Week 0 followed by 80 mg adalimumab on Week 2 achieves mean serum adalimumab trough concentrations of approximately 12 mcg/mL at Week 2 and Week 4. Mean steady-state trough levels of approximately 7 mcg/mL were observed at Week 24 and Week 56 in Crohn’s disease patients who received a maintenance dose of adalimumab 40 mg every other week.
Population pharmacokinetic analysis in patients with Crohn’s disease revealed a lower apparent clearance of adalimumab as compared to patients with rheumatoid arthritis.
In patients with ulcerative colitis, a loading dose of 160 mg adalimumab on Week 0 followed by 80 mg adalimumab on Week 2 achieved serum adalimumab trough concentrations of 11.8 ± 4.0 mcg/mL at Week 2 (n=167) and 12.3 ± 5.4 mcg/mL at Week 4 (n=160). At Week 52, trough levels of 8.0 ± 6.1 mcg/mL were observed in UC patients who received a maintenance dose of 40 mg adalimumab every other week (n=101). Trough levels at Week 52 were 10.8 ± 7.5 mcg/mL in UC patients achieving remission (n=39) and 6.2 ± 4.2 mcg/mL in UC patients not achieving remission (n=62).
In patients with HS, a dose of 160 mg adalimumab on Week 0 followed by 80 mg adalimumab on Week 2 achieved serum adalimumab trough concentrations of approximately 7 to 8 mcg/mL at Week 2 and Week 4. The mean steady-state trough concentration at Week 12 through Week 36 were approximately 8 to 10 mcg/mL during adalimumab 40 mg every week treatment.
In patients with psoriasis, the mean steady-state trough concentration was 5 mcg/mL during adalimumab 40 mg every other week monotherapy treatment.
In patients with uveitis, a loading dose of 80 mg adalimumab on Week 0 followed by 40 mg adalimumab every other week starting at Week 1, resulted in mean steady-state concentrations of approximately 8 to 10 mcg/mL.
Absorption
The maximum serum concentration (Cmax) and the time to reach the maximum concentration (Tmax) were 4.7 ± 1.6 mcg/mL and 131 ± 56 hours respectively, following a single 40 mg subcutaneous administration of adalimumab to healthy adult subjects. The average absolute bioavailability of adalimumab estimated from three studies following a single 40 mg subcutaneous dose was 64%. The pharmacokinetics of adalimumab were linear over the dose range of 0.5 to 10.0 mg/kg following a single intravenous dose.
Distribution
Adalimumab injection concentrations in the synovial fluid from five rheumatoid arthritis patients ranged from 31 to 96% of those in serum.
Metabolism
No formal studies have been conducted to evaluate the metabolism of adalimumab. However, as adalimumab is an IgG1 antibody of entirely human sequences, it is expected that its metabolism would follow the course of other IgG molecules.
Elimination
No formal studies have been conducted to evaluate the excretion of adalimumab. However, as adalimumab is an IgG1 antibody of entirely human sequences, it is expected that its excretion would follow the course of other IgG molecules.
Special Populations and Conditions
- Pediatrics
Adalimumab injection has not been studied in pediatric patients with polyarticular JIA <2 years of age or in patients with a weight <10 kg.
There are no clinical trials with adalimumab in adolescent patients (12 to 17 years of age) with hidradenitis suppurativa (HS). Use of adalimumab in adolescent patients is supported by evidence from adequate and well-controlled studies of adalimumab in adult HS patients with supplemental pharmacokinetic modeling and simulation. The use of adalimumab has not been established in patients younger than 12 years of age with HS.
Adalimumab has not been studied in pediatric patients with uveitis <2 years of age. Very limited data are available for pediatric patients with uveitis between 2 and <3 years of age.
- Geriatrics
Population pharmacokinetic analyses in patients with rheumatoid arthritis revealed that there was a trend toward lower clearance with increasing age in patients aged 40 to >75 years of age.
- Sex
Population pharmacokinetic analyses in patients with rheumatoid arthritis revealed that no gender-related pharmacokinetic differences were observed after correction for a patient’s body weight.
- Ethnic Origin
No differences in immunoglobulin clearance would be expected among races. From limited data in non-Caucasians, no important kinetic differences were observed for adalimumab.
- Hepatic Insufficiency
No pharmacokinetic data are available in patients with hepatic impairment.
- Renal Insufficiency
No pharmacokinetic data are available in patients with renal impairment.
- Disease States
Healthy volunteers and patients with rheumatoid arthritis displayed similar adalimumab pharmacokinetics. Population pharmacokinetic analyses predicted minor increases in apparent clearance in patients receiving doses lower than the recommended dose and in patients with high rheumatoid factor or C-reactive protein (CRP) concentrations. These increases are not likely to be clinically important. See 4.1 Dosing Considerations, Disease States.
11 STORAGE, STABILITY AND DISPOSAL
Idacio (adalimumab injection) must be refrigerated between 2°C and 8°C. Store in original carton until time of administration. DO NOT FREEZE. Protect from light. Do not use beyond the expiration date.
The patient has the option to store Idacio in prefilled syringes and auto-injector pen at temperatures up to a maximum of 25°C for a single period of up to 28 days. Idacio stored at temperatures up to a maximum of 25°C must be discarded if not used within the 28-day period.
Idacio, in all of its presentations, does not contain preservatives. Therefore, unused portions of the drug remaining in the container should be discarded.
12 SPECIAL HANDLING INSTRUCTIONS
Any unused product or waste material should be disposed of in accordance with local requirements.
A puncture-resistant container for disposal of needles and syringes (including the auto-injector) should be used. Patients or caregivers should be instructed in the handling technique as well as proper syringe and needle disposal and be cautioned against reuse of these items.
A healthcare professional (e.g., doctor, nurse or pharmacist) should be consulted for instructions on how to properly dispose of used needles, syringes (including the auto-injector). Special provincial or local laws regarding the proper disposal of needles, syringes and auto-injector should be followed. Needles, and syringes (including the auto-injector) should NEVER be thrown in the household trash or recycling bin.
- Used needles and syringes (including the auto-injector) should be placed in a container made especially for this purpose (sharps container), or a hard-plastic container with a screw-on cap or metal container with a plastic lid labelled “Used Syringes”. Glass or clear plastic containers should not be used.
- The container should always be kept out of the reach of children.
- When the container is about two-thirds full, the cap or lid should be taped down so that it does not come off. The container should be disposed of as instructed by a healthcare professional. CONTAINERS SHOULD NEVER BE THROWN IN THE HOUSEHOLD TRASH OR RECYCLING BIN.
- Unless otherwise instructed by a healthcare professional, used alcohol pads (not included in Idacio carton) may be placed in the trash. Dose trays and covers may be recycled.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name:
adalimumab
Chemical name:
Not applicable. Adalimumab injection is not a chemical. It is an immunoglobulin (recombinant human IgG1 monoclonal antibody).
Molecular formula and molecular mass:
Adalimumab injection consists of 1,330 amino acids and has an apparent molecular weight of approximately 148 kilodaltons (kDa).

Structural formula:
Physicochemical properties:
Adalimumab is an IgG antibody composed of two kappa light chains each with a molecular weight of approximately 24 kDa and two IgG1 heavy chains each with a molecular weight of approximately 49 kDa for a total apparent molecular weight of 148 kDa.
Idacio (adalimumab injection) is a clear and colorless, sterile, preservative free solution. Each single-dose Idacio contains a 40 mg/0.8 mL solution of adalimumab injection, with glacial acetic acid, trehalose, polysorbate 80, sodium chloride, Sodium hydroxide and Water for Injection.
Product characteristics:
Idacio (adalimumab injection) is a recombinant human immunoglobulin (IgG1) monoclonal antibody specific for human tumor necrosis factor (TNF). Adalimumab is an antibody with human derived heavy and light chain variable regions and human IgG1:κ constant regions. Adalimumab injection is produced by recombinant DNA technology in a mammalian cell expression system and is purified by a process that includes specific viral inactivation and removal steps. It consists of 1,330 amino acids and has a molecular weight of approximately 148 kDa.
14 CLINICAL TRIALS
14.5 Clinical Trials - Reference Biologic Drug
Adults
Rheumatoid Arthritis
The efficacy and safety of adalimumab injection were assessed in five randomized, double-blind studies in patients ≥18 years of age with active rheumatoid arthritis diagnosed according to the American College of Rheumatology (ACR) criteria. Patients had at least six swollen and nine tender joints. Adalimumab injection was administered subcutaneously in combination with methotrexate (12.5 to 25 mg, Studies DE009, DE019 and DE013), or as monotherapy (Studies DE011 and DE013), or with other disease-modifying anti-rheumatic drugs (DMARDs) (Study DE031).
Table 17 summarizes the controlled clinical trials that were done in patients with active rheumatoid arthritis.
Table 17 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Rheumatoid Arthritis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Gender (% Female) |
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Gender (% Female) |
DE009 (RA I) | Multicenter, double-blind, randomized, placebo-controlled | Adalimumab injection 20 mg, 40 mg or 80 mg; eow | 200 | 54.8 ± 11.9 | 75.5 |
Placebo Subcutaneous 24 weeks | 60 | 55.2 ± 10.9 | 83.3 | ||
DE011 (RA II) | Multicenter, double-blind, randomized, placebo-controlled | Adalimumab injection 20 mg or 40 mg; ew or eow | 434 | 53.0 ± 12.3 | 77.4 |
Placebo Subcutaneous 26 weeks | 110 | 53.5 ± 13.2 | 77.3 | ||
| DE019 (RA III) | Multicenter, double-blind, randomized, placebo-controlled | Adalimumab injection 20 mg ew or 40 mg eow | 419 | 56.2 ± 12.1 | 75.9 |
Placebo Subcutaneous 52 weeks | 200 | 55.6 ± 12.0 | 73.0 | ||
| Open-label extension | Adalimumab injection 40 mg eow up to 10 years | 457 | 55.7 ± 12.02 | 74.7 | |
DE031 (RA IV) | Multicenter, double-blind, randomized, placebo-controlled | Adalimumab injection 40 mg eow | 315 | 55.2 ± 12.7 | 80.0 |
Placebo Subcutaneous 24 weeks | 315 | 55.7 ± 12.4 | 79.7 | ||
| DE009, DE011, DE019, DE031 Combined | Multicenter, double-blind, randomized, placebo-controlled | Adalimumab injection Placebo | 1368 | 54.7 ± 12.3 | 77.3 |
| 685 | 55.3 ± 12.3 | 77.7 | |||
DE013 (RA V) | Phase 3, multicenter, double-blind, active comparator-controlled, parallel-group | Adalimumab injection 40 mg eow | 274 | 52.1 ± 13.5 | 77.4 |
| Adalimumab injection 40 mg eow + MTX ew | 268 | 51.9 ± 14.0 | 72.0 | ||
MTX ew Subcutaneous and oral 104 weeks | 257 | 52.0 ± 13.1 | 73.9 | ||
| Definition(s): ew=every week; eow=every other week; MTX=methotrexate | |||||
Mean ages across the four studies ranged from 53.0 years (adalimumab injection group, Study DE011) to 56.2 years (adalimumab injection group, Study DE019). The mean age in Study DE013 was 51.9 years (adalimumab injection + methotrexate group) to 52.0 years (methotrexate group). Mean weight ranged from 68.5 kg (adalimumab injection group, Study DE011) to 80.3 kg (placebo group, Study DE019). The mean weight in Study DE013 was 74.4 kg (adalimumab injection group) to 76.8 kg (adalimumab injection + methotrexate group). As expected, based on the demographics of the disease, patients were predominantly female, with the percentage of female patients ranging from 73.0% (placebo group, Study DE019) to 83.3% (placebo group, Study DE009). Similarly, the percentage of females in Study DE013 ranged from 72.0% (adalimumab injection + methotrexate group) to 77.4% (adalimumab injection group). Patients were predominantly Caucasian, with the percentage of Caucasian patients ranging from 75.0% (placebo group, Study DE009) to 99.1% (placebo group, Study DE011). The percentage of Caucasian patients in Study DE013 ranged from 93.3% (adalimumab injection + methotrexate group) to 94.2% (methotrexate group). The high percentage of Caucasian patients in Study DE011 was consistent with the populations of the geographic regions in which this study was conducted (i.e., Europe, Canada, and Australia). Overall, the demographic characteristics of the study patients were fairly representative of rheumatoid arthritis in the general population. There were no notable differences between the studies in any of the demographic characteristics analyzed.
Description of Clinical Studies
Adalimumab injection was evaluated in over 3,000 patients in all rheumatoid arthritis clinical trials. Some patients were treated for up to 10 years. The efficacy and safety of adalimumab injection were assessed in five randomized, double-blind, well-controlled studies.
Study DE009 evaluated 271 patients with moderately to severely active rheumatoid arthritis who had failed therapy with at least one but no more than four DMARDs and had inadequate response to methotrexate.
Study DE011 evaluated 544 patients with moderately to severely active rheumatoid arthritis who had failed therapy with at least one DMARD. Doses of placebo, 20 or 40 mg of adalimumab injection were given by subcutaneous injection as monotherapy every other week or weekly for 26 weeks.
Study DE019 evaluated 619 patients with moderately to severely active rheumatoid arthritis who had an inadequate response to methotrexate. Patients received placebo, 40 mg of adalimumab injection every other week with placebo injections on alternate weeks, or 20 mg of adalimumab injection weekly for up to Week 52. Study DE019 had an additional primary endpoint at Week 52 of inhibition of disease progression (as detected by X-ray results). Upon completion of the first 52 weeks, 457 patients enrolled in an open-label extension phase in which 40 mg of adalimumab injection was administered every other week for up to ten years.
202 patients completed 10 years of the study; the efficacy demonstrated at 5 years (reduction in signs and symptoms of RA, improvement in physical function, inhibition of structural joint damage, and rates of clinical response including remission) was maintained through 10 years with continued adalimumab injection in these patients. For efficacy results in these patients, see 14.5 Clinical Trials – Reference Biologic Drug, Adult, Rheumatoid Arthritis, Study Results, Clinical Response, Studies DE009, DE011 And DE019; Radiographic Response; and Quality of Life and Physical Function Response. For a description of safety in these patients, see 8.1 Adverse Reaction Overview.
Study DE031 assessed safety in 636 patients with moderately to severely active rheumatoid arthritis who were either DMARD-naïve or were permitted to remain on their pre-existing rheumatologic therapy provided that therapy was stable for a minimum of 28 days. Patients were randomized to 40 mg of adalimumab injection or placebo every other week for 24 weeks.
Study DE013 evaluated 799 patients with moderate to severely active early rheumatoid arthritis (disease duration less than three years) who were ≥18 years old and methotrexate naïve. This study compared the efficacy of adalimumab injection + methotrexate combination therapy and methotrexate monotherapy in reducing the signs and symptoms and rate of progression of joint damage in rheumatoid arthritis. Patients were randomized to receive adalimumab injection 40 mg every other week + methotrexate combination therapy, adalimumab injection 40 mg every other week monotherapy, or methotrexate given weekly, for 104 weeks.
Study Results
Clinical Response
Studies DE009, DE011 and DE019
The percent of adalimumab injection-treated patients achieving ACR 20/50/70 responses was consistent across all three trials. The results of the three trials are summarized in Table 18.
Table 18 ACR Responses in Placebo-Controlled Trials (Percent of Patients)
| Response | Study DE009* | Study DE011* | Study DE019* | |||||
Placebo + MTX | Adalimumab injection 40 mg eow + MTX | Placebo | Adalimumab injection 40 mg eow | Adalimumab injection 40 mg ew | Placebo + MTX | Adalimumab injection 40 mg eow + MTX | ||
| N=60 | N=63 | N=110 | N=113 | N=103 | N=200 | N=207 | ||
| ACR 20 | 6 months | 13.3% | 65.1%** | 19.1% | 46.0%** | 53.4%** | 29.5% | 63.3%** |
| 12 months | NA | NA | NA | NA | NA | 24.0% | 58.9%** | |
| ACR 50 | 6 months | 6.7% | 52.4%** | 8.2% | 22.1%** | 35.0%** | 9.5% | 39.1%** |
| 12 months | NA | NA | NA | NA | NA | 9.5% | 41.5%** | |
| ACR 70 | 6 months | 3.3% | 23.8%** | 1.8% | 12.4%** | 18.4%** | 2.5% | 20.8%** |
| 12 months | NA | NA | NA | NA | NA | 4.5% | 23.2%** | |
* Study DE009 at Week 24, Study DE011 at Week 26, and Study DE019 at Weeks 24 and 52 ** p <0.01 for adalimumab injection versus placebo Definition(s): MTX=methotrexate; ACR=American College of Rheumatology | ||||||||
The results of the components of the ACR response criteria for Studies DE011 and DE019 are shown in Table 19. ACR response rates and improvement in all components of ACR response were maintained to Week 104. Over the two years in Study DE019, 24% of adalimumab injection patients receiving 40 mg every other week achieved a major clinical response, defined as maintenance of an ACR 70 response over a 6-month period. ACR responses were maintained in similar proportions of patients for up to five years with continuous adalimumab injection treatment in the open-label portion of Study DE019.
Table 19 Components of ACR Response in Studies DE011 and DE019
Parameter (median) | Study DE011 | Study DE019 | |||||||||||||||||||||||||||||
| Placebo | Adalimumab injection 40 mg eow | Placebo + MTX | Adalimumab injection 40 mg eow + MTX | ||||||||||||||||||||||||||||
| N=110 | N=103 | N=200 | N=207 | ||||||||||||||||||||||||||||
| Baseline | Week 26 | Baseline | Week 26 | Baseline | Week 24 | Week 52 | Baseline | Week 24 | Week 52 | ||||||||||||||||||||||
| Number of tender joints (Scale 0 to 68) | 35 | 26 | 31 | 16* | 26 | 15 | 15 | 24 | 8.0* | 6.0* | |||||||||||||||||||||
| Number of swollen joints (Scale 0 to 66) | 19 | 16 | 18 | 10* | 17 | 11 | 11 | 18 | 5.0* | 4.0* | |||||||||||||||||||||
| Physician global assessment disease activity† | 7 | 6.1 | 6.6 | 3.7* | 6.3 | 3.5 | 3.8 | 6.5 | 2.0* | 1.6* | |||||||||||||||||||||
| Patient global assessments disease activity† | 7.5 | 6.3 | 7.5 | 4.5* | 5.4 | 3.9 | 4.3 | 5.2 | 2.0* | 1.8* | |||||||||||||||||||||
| Pain† | 7.3 | 6.1 | 7.3 | 4.1* | 6 | 3.8 | 4.6 | 5.8 | 2.1* | 1.9* | |||||||||||||||||||||
| Disability index (HAQ)‡ | 2 | 1.9 | 1.9 | 1.5* | 1.5 | 1.25 | 1.25 | 1.5 | 0.75* | 0.75* | |||||||||||||||||||||
| CRP (mg/dL) | 3.9 | 4.3 | 4.6 | 1.8* | 1 | 0.9 | 0.9 | 1 | 0.40* | 0.40* | |||||||||||||||||||||
† Visual analogue scale; 0=best; 10=worst ‡ Disability index of the Health Assessment Questionnaire (HAQ); 0=best; 3=worst, measures the patient’s ability to perform the following: dress/groom, arise, eat, walk, reach, grip, maintain hygiene, and maintain daily activity * p <0.001 for adalimumab injection versus placebo, based on mean change from baseline Definition(s): MTX=methotrexate; CRP=C-reactive protein | |||||||||||||||||||||||||||||||
The time course of ACR 20 response for Study DE019 is shown in Figure 2. In Study DE019, 85% of patients with ACR 20 responses at Week 24 maintained the response at Week 52. The time course of ACR 20 response for Studies DE009 and DE011 were similar.
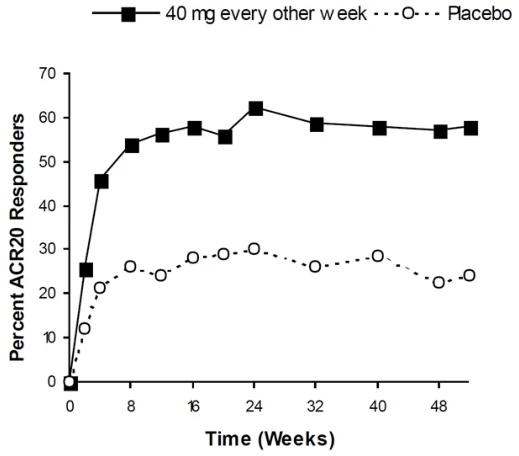
Figure 2. Study DE019 ACR 20 Responses Over 52 Weeks
In the open-label extension for Study DE019, durable and sustained ACR 20, 50 and 70 responses have been observed through 5 and 10 years. Of 207 patients, 114 patients continued on adalimumab injection 40 mg every other week for 5 years. Among those, 86 patients (75.4%) had ACR 20 responses; 72 patients (63.2%) had ACR 50 responses; and 41 patients (36%) had ACR 70 responses. Of 207 patients, 81 patients continued on adalimumab injection 40 mg every other week for 10 years. Among those, 64 patients (79.0%) had ACR 20 responses; 56 patients (69.1%) had ACR 50 responses; and 43 patients (53.1%) had ACR 70 responses.
Study DE031
In Study DE031, 53% of patients treated with adalimumab injection 40 mg every other week plus standard of care had an ACR 20 response at Week 24 compared to 35% on placebo plus standard of care (p <0.001). No unique adverse reactions related to the combination of adalimumab injection and other DMARDs were observed.
In all four studies, adalimumab injection-treated patients achieved ACR 20/50/70 responses faster and more often than placebo-treated patients. In Study DE009, there was a statistically significant difference in ACR 20 responses at Week 1 (first study visit) between patients treated with adalimumab injection (26.0%) and placebo (5.0%). Statistically significant differences in ACR 20 responses were also seen in Studies DE011, DE019 and DE031 at Week 2 (first study visit) between patients treated with adalimumab injection (36.4, 29.1 and 33.7%, respectively) and placebo (7.3, 13.0 and 8.6% respectively). A similar pattern of the time to first ACR 50 and 70 responses was noted in all four studies.
Study DE013
In Study DE013, for early rheumatoid arthritis patients who were MTX naïve, the combination therapy with adalimumab injection + MTX led to faster and significantly greater ACR responses than MTX monotherapy at Week 52, and responses were sustained at Week 104. The clinical responses for Study DE013 are presented in Table 20.
At Week 52, all individual components of the ACR response criteria improved with adalimumab injection + MTX therapy, and improvements were maintained to Week 104.
Over the two-year study, 48.5% of patients who received adalimumab injection + MTX combination therapy achieved a major clinical response (ACR 70 for six continuous months) compared to 27.2% of patients who received MTX monotherapy (p <0.001).
Table 20 Clinical Responses in Study DE013 (All Randomized Subjects)
| Response | MTXa N=257 (%) | Adalimumab injectionb N=274 (%) | Adalimumab injection + MTX N=268 (%) | ||||
| ACR 20 | Week 52 | 62.6 | 54.4 | 72.8 | |||
| Week 104 | 56.0 | 49.3 | 69.4 | ||||
| ACR 50 | Week 52 | 45.9 | 41.2 | 61.6 | |||
| Week 104 | 42.8 | 36.9 | 59.0 | ||||
| ACR 70 | Week 52 | 27.2 | 25.9 | 45.5 | |||
| Week 104 | 28.4 | 28.1 | 46.6 | ||||
| Major Clinical Responsec | 27.2 | 24.5 | 48.5 | ||||
a. p <0.05 for adalimumab injection + MTX versus MTX for ACR 20 p <0.001 for adalimumab injection + MTX versus MTX for ACR 50 and 70 and major Clinical Response b. p <0.001 for adalimumab injection + MTX versus adalimumab injection c. Major Clinical Response is achieving ACR 70 response for a continuous six-month period Definition(s): MTX=methotrexate; ACR=American College of Rheumatology | |||||||
At Week 52 and Week 104 of treatment in Study DE013, adalimumab injection + MTX combination therapy was superior to MTX monotherapy in achieving a low disease state in patients with recently diagnosed moderate to severe rheumatoid arthritis, as demonstrated by the number of patients who achieved clinical remission [disease activity score (DAS28) <2.6] at Week 52 and change from baseline in DAS28 at Week 52 and Week 104.
DAS28 responses for Study DE013 are presented in Table 21.
Table 21 Change in DAS28 from Baseline at Weeks 52 and 104 in Study DE013 (All Randomized Subjects)
| DAS28 | MTX | Adalimumab injection | Adalimumab injection + MTX | |||||||||
| DAS28 | MTX | Adalimumab injection | Adalimumab injection + MTX | |||||||||
| N=257 | N=274 | N=268 | ||||||||||
| N=257 | N=274 | N=268 | ||||||||||
| Week 52 | n | 184 | 185 | 206 | ||||||||
| Baseline (mean) | 6.3 | 6.4 | 6.3 | |||||||||
| Change at Week 52 (mean ± SD) | -2.8 ± 1.4a | -2.8 ± 1.5b | -3.6 ± 1.3 | |||||||||
| % of subjects in remission (DAS28 <2.6) at Week 52 | 20.6% a | 23.4% b | 42.9% | |||||||||
| Week 104 | n | 161 | 158 | 191 | ||||||||
| Baseline (mean) | 6.3 | 6.3 | 6.3 | |||||||||
| Change at Week 104 (mean ± SD) | -3.1 ± 1.4a | -3.2 ± 1.4b | -3.8 ± 1.3 | |||||||||
| % of subjects in remission (DAS28 <2.6) at Week 104 | 24.9% | 25.2% | 49.3% | |||||||||
a. p <0.001 for adalimumab injection + MTX versus MTX b. p <0.001 for adalimumab injection + MTX versus adalimumab injection Definition(s): MTX=methotrexate; DAS=disease activity score; SD=standard deviation | ||||||||||||
Radiographic Response
In Study DE019, where adalimumab injection-treated patients had a mean duration of rheumatoid arthritis of approximately 11 years, structural joint damage was assessed radiographically and expressed as change in total Sharp score (TSS) and its components, the erosion score and joint space narrowing (JSN) score at Month 12 compared to baseline. At baseline, the median TSS was approximately 55 in the placebo and 40 mg every other week groups. The 12-month results are shown in Table 22. Adalimumab injection + MTX-treated patients demonstrated less radiographic progression than patients receiving MTX alone at Week 52.
Table 22 Radiographic Mean Changes Over 12 Months in Study DE019 with Background Methotrexate
| LOCF | Placebo + MTX | Adalimumab injectiona + MTX | Adalimumab injectiona + MTX and Placebo + MTX | p-value | |||||||
| N=200 | N=207 | (95% CI**) | |||||||||
| Change in Modified Total Sharp Score (Mean) | 2.7 | 0.1 | -2.6 (1.4, 3.8) | <0.001* | |||||||
| Change in Erosions (Mean) | 1.6 | 0 | -1.6 (0.9, 2.2) | <0.001 | |||||||
| Change in JSN Score (Mean) | 1 | 0.1 | -0.9 (0.3, 1.4) | 0.002 | |||||||
a. 40 mg administered every other week * Based on analysis of ranked ANCOVA ** 95% confidence intervals for the differences in change scores between methotrexate and adalimumab injection Definition(s): MTX=methotrexate; LOCF=last observation carried forward; JSN=joint space narrowing; CI=confidence interval | |||||||||||
Data from the open-label extension of Study DE019 indicate that the reduction in rate of progression of structural damage is maintained for 8 and 10 years in a subset of patients. At 8 years, 81 of 207 patients originally treated with 40 mg adalimumab injection every other week were evaluated radiographically. Among those, 59.3% (48 patients) showed no progression of structural damage defined by a change from baseline in the mTSS of 0.5 or less. At 10 years, 79 of 207 patients originally treated with 40 mg adalimumab injection every other week were evaluated radiographically. Among those, 50.6% (40 patients) showed no progression of structural damage defined by a change from baseline in the mTSS of 0.5 or less.
In Study DE013, adalimumab injection-treated patients had a mean duration of rheumatoid arthritis of less than nine months and had not previously received methotrexate. Structural joint damage was assessed radiographically and expressed as change in modified total Sharp score (TSS). The Week 52 results are shown in Table 23. A statistically significant difference for change in modified total Sharp score, erosion score and JSN were observed at Week 52 and maintained at Week 104.
Table 23 Radiographic Mean Change (95% Confidence Interval) in Study DE013
| Response | MTXa | Adalimumab injectiona,b | Adalimumab injection + MTX |
| N=257 | N=274 | N=268 | |
| Week 52 | |||
| Total Sharp Score | 5.7 (4.2, 7.3) | 3.0 (1.7, 4.3) | 1.3 (0.5, 2.1) |
| Erosion Score | 3.7 (2.7, 4.8) | 1.7 (1.0, 2.4) | 0.8 (0.4, 1.2) |
| JSN Score | 2.0 (1.2, 2.8) | 1.3 (0.5, 2.1) | 0.5 (0.0, 1.0) |
| Week 104 | |||
| Total Sharp Score | |||
| 10.4 (7.7, 13.2) | 5.5 (3.6, 7.4) | 1.9 (0.9, 2.9) | |
| Erosion Score | 6.4 (4.6, 8.2) | 3.0 (2.0, 4.0) | 1.0 (0.4, 1.6) |
| JSN Score | 4.1 (2.7, 5.4) | 2.6 (1.5, 3.7) | 0.9 (0.3, 1.5) |
a. p <0.001 for adalimumab injection + MTX versus MTX at Week 52 and Week 104 and for adalimumab injection + MTX versus adalimumab injection at Week 104 b. p <0.01 for adalimumab injection + MTX versus adalimumab injection at Week 52 Definition(s): MTX=methotrexate; JSN=joint space narrowing | |||
The percentage of patients without progression (change from baseline in modified total Sharp score ≤0.5) was significantly higher with adalimumab injection + MTX combination therapy compared to MTX monotherapy at Week 52 (63.8 and 37.4% respectively, p <0.001) and Week 104 (61.2 and 33.5% respectively, p <0.001).
Quality of Life and Physical Function Response
In Studies DE009, DE011, DE019 and DE031, adalimumab injection showed significantly greater improvement than placebo in the disability index of Health Assessment Questionnaire (HAQ) from baseline to the end of study, and significantly greater improvement than placebo in the health outcomes as assessed by the Short Form Health Survey (SF-36). Improvement was seen in both the Physical Component Summary (PCS) and the Mental Component Summary (MCS).
In Study DE019, the mean (CI) improvement in HAQ from baseline at Week 52 was -0.60 (-0.65, -0.55) for the adalimumab injection patients and -0.25 (-0.33, -0.17) for placebo + MTX (p <0.001) patients. Eighty-two percent (82%) of adalimumab injection-treated patients who achieved a 0.5 or greater improvement in HAQ at Week 52 in the double-blind portion of the study maintained that improvement through Week 104 of open-label treatment, and a similar proportion of patients maintained this response through Week 260 (five years) and Week 520 (10 years). After five years, the proportion of subjects who were HAQ responders at the 0.22, 0.50, 0.75 and 1.0 levels were 76.5, 60.0, 47.5 and 30.8% respectively. A total of 149 patients who received adalimumab injection for 10 years were assessed for HAQ. After 10 years, the proportions of patients who were HAQ responders at the 0.22, 0.50, 0.75 and 1.0 levels were 73.8 (n=110), 57.0 (n=85), 44.3 (n=66) and 26.2% (n=39) respectively. Improvement in SF-36 was measured and maintained up to Week 156 (3 years).
In Study DE013, the active comparator-controlled study in early rheumatoid arthritis, the improvement in the HAQ disability index, and the physical component of the SF-36 showed greater improvement (p <0.001) for the adalimumab injection + MTX combination therapy versus the MTX monotherapy at Week 52, which was maintained through Week 104.
At Week 52 and Week 104 of treatment, 69.4% (186/268) and 63.8% (171/268) of subjects, respectively, treated with adalimumab injection + MTX combination therapy had a decrease (i.e., improvement) in the disability index of the HAQ of ≥0.3 units. In comparison, 61.5% (158/257; p=0.562) and 53.3% (137/257; p=0.0146) of subjects treated with MTX monotherapy, and 55.1% (151/274; p <0.001) and 48.2% (132/274; p <0.001) of subjects treated with adalimumab injection monotherapy had a decrease in the disability index of the HAQ of ≥0.3 units at Weeks 52 and 104, respectively.
Psoriatic Arthritis
The efficacy of adalimumab injection was assessed in two randomized, double-blind, placebo-controlled studies in 413 patients. The primary study treated 313 adult patients with moderately to severely active psoriatic arthritis who had an inadequate response to nonsteroidal anti-inflammatory drug (NSAID) therapy. Of the 313 treated in this study, 158 (50.5%) were described as taking MTX at the time of randomization. Doses of adalimumab injection 40 mg every other week were administered for 24 weeks. Table 24 summarizes the controlled clinical trials that were done in patients with active psoriatic arthritis.
Table 24 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Psoriatic Arthritis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Sex |
|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Sex |
| (n) | (Range) | (%Female) | |||
| (n) | (Range) | (%Female) | |||
| M02-518 (PsA I) | Multicenter, double-blind, randomized, placebo-controlled, stratified by MTX use and extent of psoriasis (≥3% or <3% BSA) | Adalimumab injection 40 mg eow | 151 | 48.6 ± 12.5 | 43.7 |
| Placebo | 162 | 49.2 ± 11.1 | 45.1 | ||
Subcutaneous 24 weeks | |||||
| M02-570 (PsA II) | Multicenter, double-blind, randomized, placebo-controlled, stratified by DMARD use (yes, no) | Adalimumab injection 40 mg eow | 51 | 50.4 ± 11.0 | 43.1 |
| Placebo | 49 | 47.7 ± 11.3 | 49.0 | ||
Subcutaneous 24 weeks | |||||
M02-518 and M02-570 | Multicenter, double-blind, randomized, placebo-controlled, stratified with MTX (M02-518), and DMARDs (M02-570) | Adalimumab injection 40 mg eow | 202 | 49.1 ± 12.2 | 43.6 |
| Placebo | 211 | 48.9 ± 11.2 | 46.0 | ||
Subcutaneous 24 weeks | |||||
| Definition(s): eow=every other week; MTX=methotrexate; BSA=body surface area; DMARDs=disease-modifying anti-rheumatic drugs | |||||
Mean ages across the two studies ranged from 47.7 years (placebo group, Study M02-570) to 50.4 years (adalimumab injection group, Study M02-570). Mean weight ranged from 85.5 kg (placebo group, Study M02-518) and 91.5 kg (adalimumab injection group, Study M02-570). The percentage of females ranged from 43.1% (adalimumab injection group, Study M02-570) and 45.1% (placebo group, Study M02-518). Patients were predominantly Caucasian, with the percentage of Caucasian patients ranging from 93.8% (placebo group, Study M02-518) to 98.0% (adalimumab injection group, Study M02-570). There were no notable differences between the studies in any of the demographic characteristics analyzed. Upon completion of both studies, 383 patients enrolled in an open-label extension study (Table 25) in which adalimumab injection 40 mg is administered every other week.
Table 25 Summary of Open-Label Clinical Trials Evaluating Long-Term Safety and Efficacy in Patients with Psoriatic Arthritis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age (Range) | Sex |
| (n) | (Years) | (% Female) | |||
| M02-537 (PsA III) | Multicenter, open-label, multi-national continuation of studies M02-518 and M02-570. | Adalimumab injection 40 mg eow Subcutaneous 120 weeks or when commercially available, whichever is later | 395 | 49.0 ± 11.7 (20.0 to 88.0) | 44.6 |
| Definition(s): eow=every other week | |||||
Description of Clinical Studies
Study M02-518 evaluated the effectiveness and safety of adalimumab injection either alone or in combination with concomitant methotrexate in subjects with moderately to severely active PsA who have had an inadequate response or intolerance to NSAID therapy.
Study M02-570 evaluated the effectiveness and safety of adalimumab injection either alone or in combination with any concomitant DMARD (except cyclosporine or tacrolimus) in subjects with moderately to severely active psoriatic arthritis who have had an inadequate response to DMARD therapy.
Study M02-537 evaluates the long-term safety and efficacy of adalimumab injection 40 mg every other week in the treatment of psoriatic arthritis in subjects who completed the controlled Studies M02-518 and M02-570.
Study Results
Clinical Response
Studies M02-518, M02-570 and M02-537
Adalimumab injection was superior to placebo in all measures of disease activity (p <0.001) as shown in Table 26 and Table 27. Among patients with psoriatic arthritis who received adalimumab injection, the clinical responses were apparent at the time of the first visit (Week 2), significant at Week 12, and maintained at Week 24 in the double-blind period of the study. Table 26 presents data from the ongoing open-label study regarding improvement in arthritic manifestations of psoriatic arthritis.
Patients with a psoriasis involvement of at least three percent body surface area (BSA) were evaluated for Psoriatic Area and Severity Index (PASI) responses. In these patients, the skin lesions of psoriasis were improved with adalimumab injection, relative to placebo, as measured by the PASI. Results were similar with and without concomitant methotrexate therapy. The small number of patients with moderate to severe psoriasis requires additional data to adequately assess the PASI response.
Table 26 ACR and PASI Response in Placebo-Controlled Psoriatic Arthritis Study (Study M02-518) (Percent of Patients)
| Response | Placebo N=162 | Adalimumab injection† N=151 | |
| ACR 20 | Week 12 | 14% | 58% |
| Week 24 | 15% | 57% | |
| ACR 50 | Week 12 | 4% | 36% |
| Week 24 | 6% | 39% | |
| ACR 70 | Week 12 | 1% | 20% |
| Week 24 | 1% | 23% | |
| Response | Placebo N=69 | Adalimumab injection† N=69 | |
| PASI 50 | Week 12 | 15% | 72% |
| Week 24 | 12% | 75% | |
| PASI 75 | Week 12 | 4% | 49% |
| Week 24 | 1% | 59% | |
† p <0.001 for all comparisons between adalimumab injection and placebo Definition(s): ACR=American College of Rheumatology; PASI=Psoriasis Area and Severity Index | |||
Table 27 Components of Disease Activity in Psoriatic Arthritis (Study M02-518)
| Parameter mean (median) | Placebo† | Adalimumab injection†‡ | |||||||||
| N=162 | N=151 | ||||||||||
| Baseline | Week 24 | Baseline | Week 24 | ||||||||
| Number of tender joints (Scale 0 to 78) | 25.8 (23.0) | 22.3 (17.0) | 23.3 (19.0) | 11.8 (5.0) | |||||||
| Number of swollen joints (Scale 0 to 76) | 14.6 (11.0) | 12.1 (8.0) | 13.4 (10.0) | 7.6 (3.0) | |||||||
| Physician global assessmenta | 53.2 (53.0) | 46.0 (48.0) | 53.5 (54.0) | 21.4 (16.0) | |||||||
| Patient global assessmenta | 47.2 (49.0) | 47.6 (49.0) | 47.5 (48.0) | 24.2 (18.5) | |||||||
| Paina | 47.6 (47.5) | 47.9 (49.0) | 50.6 (53.0) | 25.4 (19.0) | |||||||
| Disability index (HAQ)b | 1.0 (1.0) | 0.9 (0.8) | 1.0 (0.9) | 0.6 (0.4) | |||||||
| CRP (mg/dL)c | 1.4 (0.8) | 1.4 (0.7) | 1.4 (0.8) | 0.5 (0.2) | |||||||
† As observed analysis presented, N at Week 24 may be less than 162 for placebo or 151 for adalimumab injection ‡ p <0.001 for adalimumab injection versus placebo comparisons based on mean change from baseline a. Visual analogue scale; 0=best, 100=worst; b. Disability index of the Health Assessment Questionnaire (HAQ); 0=best, 3=worst; measures the patient’s ability to perform the following: dress/groom, arise, eat, walk, reach, grip, maintain hygiene, and maintain daily activity c. C-reactive protein (CRP) normal range: 0 to 0.287 mg/dL | |||||||||||
Radiographic Response
Radiographic changes in the hands wrists, and feet were assessed in the psoriatic arthritis study at baseline and Week 24 during the double-blind period when patients were on adalimumab injection or placebo and at Week 48 when all patients were on open-label adalimumab injection. A modified total Sharp score (mTSS), which included distal interphalangeal joints (i.e., not identical to the TSS used for rheumatoid arthritis), was used by readers blinded to treatment group to assess the radiographs.
Week 24
The mean change in modified total Sharp score was evaluated and demonstrated that adalimumab injection-treated patients had significantly less progression in their X-rays, compared to placebo-treated patients. As shown in Table 28, the mean change from baseline in both the erosion and the joint space narrowing scores in the adalimumab injection treatment group was significantly superior to placebo. As with other TNF agents, the median change in Sharp scores for both patient groups were zero.
Table 28 Radiographic Mean Changes at Week 24 in Placebo-Controlled Psoriatic Arthritis Study (Study M02-518) †
| Response | Placebo | Adalimumab injection | p-value | |||||
| N=152 | N=144 | |||||||
| Total Sharp score | 1 | -0.2 | <0.001 | |||||
| Erosion score | 0.6 | 0 | <0.001 | |||||
| JSN score | 0.4 | -0.2 | <0.001 | |||||
† Analysis of patients with X-ray films at both baseline and Week 24 Definition(s): JSN=joint space narrowing | ||||||||
Week 48
Adalimumab injection-treated patients demonstrated greater inhibition of radiographic progression at Week 48 compared to placebo-treated patients at Week 24 (see Table 29).
Table 29 Change in Modified Total Sharp Score‡ in Psoriatic Arthritis (Study M02-537)
| Response | Placebo N=141 | Adalimumab injection N=133 | |
| Week 24 | Week 24 | Week 48 | |
Modified Total Sharp Score | |||
| Baseline mean | 22.1 | 23.4 | 23.4 |
| Mean change ± SD | 0.9 ± 3.06 | -0.1 ± 1.69** | 0.1 ± 2.74** |
| Change (range) | -3.5 to 22.0 | -6.8 to 12.5 | -5.9 to 24.2 |
| Erosion Score | |||
| Baseline mean | 11.8 | 12.4 | 12.4 |
| Mean change ± SD | 0.5 ± 1.91 | 0.0 ± 0.91** | 0.1 ± 1.79* |
| Change (range) | -2.2 to 14.5 | -2.2 to 7.5 | -4.4 to 16.5 |
| JSN score | |||
| Baseline mean | 10.4 | 11.0 | 11.0 |
| Mean change ± SD | 0.4 ± 1.60 | -0.1 ± 1.06** | 0.0 ± 1.33** |
| Change (range) | -3.5 to 10.2 | -5.7 to 5.0 | -4.0 to 7.7 |
* p <0.05 for the difference between adalimumab injection, Week 48 and placebo, Week 24 (primary analysis) ** p <0.001 for the difference between adalimumab injection, Week 48 and placebo, Week 24 (primary analysis) ‡ X-rays with less than 50% assessments were imputed Definition(s): JSN=joint space narrowing; SD=standard deviation | |||
Physical Function Response
Disability and physical function were assessed in psoriatic arthritis study using Health Assessment Questionnaire Disability Index (HAQ-DI). The adalimumab injection-treated patients had significantly greater improvement in the disability index of the HAQ from baseline to Week 24, compared to placebo and were maintained up to Week 84 (see Table 30 and Table 31).
Table 30 Disability Index of the HAQ (Full Analysis Set) (Study M02-518)
| Disability Index of the HAQ | Placebo | Adalimumab injection 40 mg eow | p-valuea | ||||||||||
| N=162 | N=151 | ||||||||||||
| N | Mean ± SD | N | Mean ± SD | ||||||||||
| Week 12 | Baseline | 154 | 1.0 | 142 | 1.0 | <0.001* | |||||||
| Change Observed | 154 | -0.1 ± 0.45 | 142 | -0.4 ± 0.45 | |||||||||
| Week 24 | Baseline | 145 | 1.0 | 141 | 1.0 | <0.001* | |||||||
| Change Observed | 145 | -0.1 ± 0.42 | 141 | -0.4 ± 0.49 | |||||||||
* Statistically significant at the p=0.001 level a. p-value for differences between treatment groups from an ANOVA model with treatment group and baseline methotrexate use/extent of psoriasis (≥3% BSA, <3% BSA) as factors Definition(s): HAQ=Health Assessment Questionnaire; BSA=body surface area; eow=every other week; SD=standard deviation | |||||||||||||
Table 31 Mean Change from Baseline in Disability Index of HAQ by Visit (Observed) (Study M02-518 Subjects Randomized to adalimumab injection)
| Visit | N | Baselinea Mean | Visit Mean | Change from Baseline | ||
|---|---|---|---|---|---|---|
| Mean | Standard Deviation | Range (Min to Max) | ||||
| Week 24 | 137 | 1.0 | 0.6 | -0.4 | 0.48 | -1.8 to 1.1 |
| Week 26 | 137 | 1.0 | 0.5 | -0.4 | 0.50 | -2.1 to 0.9 |
| Week 30 | 137 | 1.0 | 0.6 | -0.4 | 0.49 | -1.9 to 1.0 |
| Week 36 | 137 | 1.0 | 0.6 | -0.4 | 0.50 | -1.9 to 1.1 |
| Week 42 | 135 | 1.0 | 0.6 | -0.4 | 0.50 | -1.9 to 1.0 |
| Week 48 | 134 | 1.0 | 0.6 | -0.4 | 0.54 | -2.3 to 0.9 |
| Week 60 | 132 | 1.0 | 0.5 | -0.4 | 0.49 | -1.9 to 0.6 |
| Week 72 | 129 | 1.0 | 0.6 | -0.4 | 0.49 | -1.9 to 0.6 |
| Week 84 | 79 | 0.9 | 0.5 | -0.4 | 0.49 | -1.9 to 0.8 |
Note: The disability index of the Health Assessment Questionnaire (HAQ) has a range from 0 to 3 with a higher score indicating a greater extent of functional limitations a. Last assessment prior to the first adalimumab injection | ||||||
A subset of the subjects is still being followed in the ongoing study.
Results from the Short Form Health Survey (SF-36) support these findings, with statistically significant Physical Component Summary (PCS) scores, as well as statistically significant pain and vitality domain scores at Week 24, which were maintained to Week 72.
Ankylosing Spondylitis
The safety and efficacy of adalimumab injection 40 mg every other week were assessed in 393 adult patients in two randomized, 24-week double-blind, placebo-controlled studies in patients with active ankylosing spondylitis who have had an inadequate response to or intolerance to one or more NSAIDs, and who may have additionally failed DMARD therapy. The larger study enrolled 315 adult patients with active ankylosing spondylitis [defined as fulfilling at least two of the following three criteria: (1) a Bath Ankylosing Spondylitis Disease Activity Index (BASDAI) score ≥4 cm, (2) a visual analogue score (VAS) for total back pain ≥40 mm, and (3) morning stiffness ≥1 hour]. The primary efficacy endpoint was percentage of ASAS 20 responders at Week 12 measured by the Assessment in Ankylosing Spondylitis (ASAS) response criteria. Additional pre-determined endpoints included: response as defined by ASAS 5/6 criteria, ASAS 40/50/70 and partial remission, Bath Ankylosing Spondylitis Metrology Index (BASMI), Maastricht Ankylosing Spondylitis Enthesitis Score (MASES), and Bath Ankylosing Spondylitis Disease Activity Index (BASDAI). The blinded period was followed by an open-label period during which patients received adalimumab injection 40 mg every other week subcutaneously for up to an additional 80 weeks.
Study Results
Clinical Response
Results showed statistically significant reduction in signs and symptoms of ankylosing spondylitis in patients treated with adalimumab injection compared to placebo in Study M03-607. Significant improvement in measures of disease activity was first observed at Week 2 and maintained through Week 24 as shown in Figure 3 and Table 32.
Patients with total spinal ankylosis were included in the larger study (n=11). Responses of these patients were similar to those without total ankylosis.
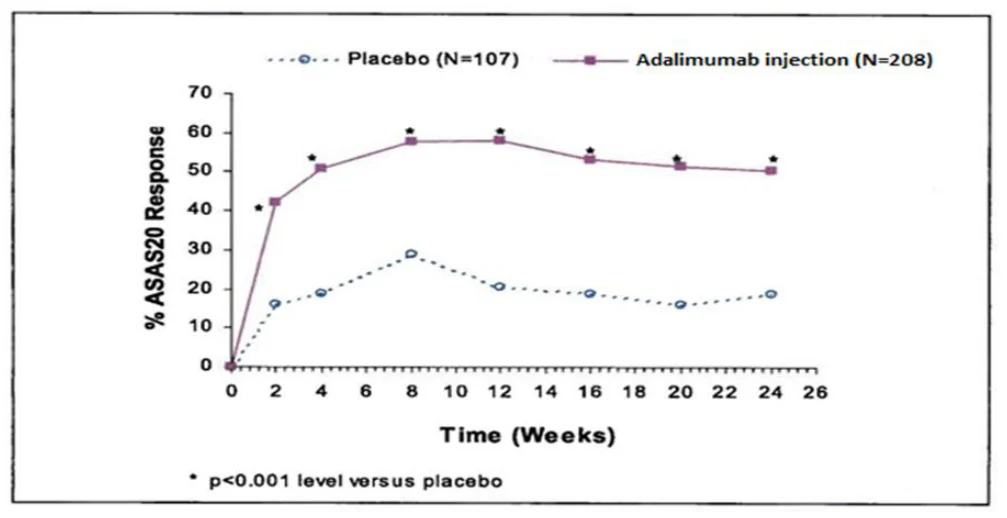
Figure 3. ASAS 20 Response by Visit, Study M03-607
At Week 12, the ASAS 20/50/70 responses were achieved by 58, 38, and 23%, respectively, of patients receiving adalimumab injection, compared to 21, 10, and 5% respectively, of patients receiving placebo (p <0.001). At Week 24, the ASAS 20/50/70 responses were achieved by 51, 35 and 24%, respectively, of patients receiving adalimumab injection, compared to 19, 11, and 8%, respectively, of patients receiving placebo (p <0.001). These results were sustained in patients receiving open-label adalimumab injection through Week 52.
In a sub-group analysis by region an adalimumab injection versus placebo treatment group difference was observed between the United States (US) and European (EU) subjects (21.7 and 50.9% respectively). This difference in the treatment effect is driven by the different placebo ASAS 20 response rates (33.3% for US versus 10.2% for EU). However, the adalimumab injection ASAS 20 response rates were 55 and 61.1% in the US and EU respectively.
A low level of disease activity [defined as a value <20 (on a scale of 0 to 100 mm) in each of the four ASAS response parameters] was achieved at Week 24 in 22% of adalimumab injection-treated patients versus 6% in placebo-treated patients (p <0.001).
Other secondary and additional measures of efficacy such as response as defined by ASAS 5/6 criteria, ASAS 40, metrology (BASMI), enthesitis (MASES), and disease activity (BASDAI) were statistically significant at Weeks 12 and 24.
Table 32 Components of Ankylosing Spondylitis Disease Activity in Study M03-607
| Parameters | Placebo | Adalimumab injection | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| N=107 | N=208 | |||||||||||||||
| Baseline | Week 24 | Baseline | Week 24 | |||||||||||||
| Mean | Mean | Mean | Mean | |||||||||||||
| ASAS 20 Response Criteria* | ||||||||||||||||
| Patient’s Global Assessment of Disease Activitya | 65 | 60 | 63 | 38 | ||||||||||||
| Total Back Pain | 67 | 58 | 65 | 37 | ||||||||||||
| Inflammationb | 6.7 | 5.6 | 6.7 | 3.6 | ||||||||||||
| BASFI | 56 | 51 | 52 | 34 | ||||||||||||
| BASDAI* Score | 6.3 | 5.5 | 6.3 | 3.7 | ||||||||||||
| CRP* | 2.2 | 2 | 1.8 | 0.6 | ||||||||||||
a. Percent of subjects with at least a 20% and 10-unit improvement measured on a visual analogue scale (VAS) with 0=“none” and 100=“severe” b. Mean of questions 5 and 6 of BASDAI * Statistically significant as p <0.001 for all comparisons between adalimumab injection and placebo at Week 24 Definition(s): BASFI=Bath Ankylosing Spondylitis Functional Index; BASDAI=Bath Ankylosing Spondylitis Disease Activity Index; CRP=C-reactive protein (mg/dL) | ||||||||||||||||
Similar results (not all statistically significant) were seen in the second randomized trial, a multicenter, double-blind, placebo-controlled study of 82 patients with ankylosing spondylitis (Study M03-606).
Patients treated with adalimumab injection achieved statistically significant greater improvement from baseline in the Ankylosing Spondylitis Quality of Life Questionnaire (ASQoL) score (-3.15 versus -0.95, p <0.001) and in the Short Form Health Survey (SF-36) Physical Component Summary (PCS) score (6.93 versus 1.55, p <0.001) compared to placebo-treated patients at Week 12, which were maintained through Week 24.
Crohn’s Disease
The safety and efficacy of multiple doses of adalimumab injection were assessed in over 1,500 adult patients with moderately to severely active Crohn’s disease (Crohn’s Disease Activity Index [CDAI] ≥220 and ≤450) in randomized, double-blind, placebo-controlled studies. Concomitant stable doses of aminosalicylates, corticosteroids, and/or immunomodulatory agents were permitted and 80% of patients continued to receive at least one of these medications.
Table 33 summarizes the controlled clinical trials and Table 34 summarizes the open-label clinical trials that were done in patients with moderately to severely active Crohn’s disease.
Table 33 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Crohn’s Disease
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Gender (% Female) |
|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) | Gender (% Female) |
| M02-403 (CD I) | Randomized, double-blind, placebo-controlled, multicenter, dose ranging study in anti-TNF naïve patients | Adalimumab injection 160 mg at Week 0 and 80 mg at Week 2; or Adalimumab injection 80 mg at Week 0 and 40 mg at Week 2; or Adalimumab injection 40 mg at Week 0 and 20 mg at Week 2 | 225 | 39 ± 12 (18 to 74) | 55.6 |
| Placebo | 74 | 37 ± 13 (19 to 74) | 50.0 | ||
Subcutaneous 4 weeks | |||||
M04-691 (CD II) | Randomized, double-blind, placebo-controlled, multicenter study in patients who had lost response to or were intolerant to infliximab | Adalimumab injection 160 mg at Week 0 and 80 mg at Week 2 | 159 | 39.4 ± 11.9 (19 to 75) | 68.6 |
| Placebo | 166 | 37.4 ± 11.9 (18 to 75) | 60.8 | ||
| Subcutaneous 4 weeks | |||||
M02-404 (CD III) | Randomized, double-blind, multicenter, placebo-controlled | Initial Open-Label: Adalimumab injection 80 mg at Week 0 and 40 mg at Week 2 Post-Randomization (Week 4): | |||
Adalimumab injection 40 mg eow | 260 | 36.8 ± 11.5 (17 to 73) | 62.7 | ||
Adalimumab injection 40 mg ew | 257 | 37.8 ± 12.1 (18 to 75) | 61.1 | ||
| Placebo | 261 | 36.9 ± 11.4 (18 to 75) | 62.1 | ||
| Not randomized Subcutaneous 56 weeks | 76 | 36.1 ± 13.6 (19 to 75) | 60.5 | ||
M05-769 (CD VI) | Randomized, double-blind, placebo-controlled, multicenter, efficacy and safety study. | Patients received OL induction therapy of adalimumab injection 160/80 mg at Weeks 0/2, and were stratified by responder status to adalimumab injection 40 mg eow or placebo for up to 52 weeks. At Week 52, patients were switched to OL Adalimumab injection 40 mg eow for up to an additional 36 weeks.) | |||
| Adalimumab injection eow | 64 | 37 (18 to 74) | 62.5 | ||
| Placebo | 65 | 37 (18 to 67) | 63.1 | ||
| Definition(s): ew=every week; eow=every other week; TNF=tumor necrosis factor; OL =open-label | |||||
Table 34 Summary of Open-Label Clinical Trials Supporting Safety and Efficacy in Patients with Crohn’s Disease
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender | ||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| (n) | (Range) | (% Female) | |||||||||
| M02-433 (CD IV) | Open-label extension of placebo-controlled Study M02-403 | Patients received OL adalimumab injection 40 mg at baseline (Week 0) and week 2. At Week 4, patients were assigned to one of three blinded treatment groups (Adalimumab injection eow, ew, or placebo) or OL adalimumab injection eow treatment, based on clinical remission status at baseline. After 1 year (Week 56), patients entered long-term extension phase up to more than 5 years (including preceding M02-403 study); those receiving blinded treatment were switched to OL adalimumab injection eow, and those in the OL group continued their OL treatment. | |||||||||
| All | 276 | 39 (18 – 74) | 54.7 | ||||||||
M04-690 (CD V) | Open-label extension of placebo-controlled Studies M04-691 or M02-404 | Patients entering from a blinded cohort were assigned to OL adalimumab injection 40 mg eow; patients entering the study from an OL cohort continued their previous dosing regimen of eow or ew. | |||||||||
| Study M02-404 cohort | 467 | All | All | ||||||||
| Study M04-691 cohort | 310 | 38 (17 to 75) | 62.4 | ||||||||
| Definition(s): ew=every week; eow=every other week; OL =open-label | |||||||||||
Description of Clinical Studies
Induction of clinical remission (defined as CDAI <150) was evaluated in two studies, Studies M02-403 and M04-691.
In Study M02-403, 299 TNF-blocker naïve patients were randomized to one of four treatment groups; the placebo group received placebo at Weeks 0 and 2, the 160/80 group received 160 mg adalimumab injection at Week 0 and 80 mg at Week 2, the 80/40 group received 80 mg at Week 0 and 40 mg at Week 2, and the 40/20 group received 40 mg at Week 0 and 20 mg at Week 2.
In Study M04-691, 325 patients who had lost response or were intolerant to infliximab were randomized to receive either 160 mg adalimumab injection at Week 0 and 80 mg at Week 2 or placebo at Weeks 0 and 2.
Maintenance of clinical remission was evaluated in Study M02-404.
In Study M02-404, 854 patients received open-label 80 mg adalimumab injection at Week 0 and adalimumab injection 40 mg at Week 2. At Week 4, patients were stratified by their responder status and previous anti-tumor necrosis factor (TNF) use (no, yes) and randomized to one of three blinded treatment groups: adalimumab injection 40 mg every other week, adalimumab injection 40 mg every week or placebo with a total study duration of 56 weeks. Patients in clinical response (decrease in CDAI ≥70) at Week 4 were stratified and analyzed separately from those not in clinical response at Week 4. Corticosteroid tapering was permitted after Week 8.
Study M05-769 assessed mucosal healing in 135 patients; patients received open-label induction therapy of adalimumab injection 160/80 mg at weeks 0/2, and were stratified by responder status to adalimumab injection 40 mg every other week (eow) or placebo for up to 52 weeks. At Week 52, patients were switched to open-label adalimumab injection 40 mg eow for up to an additional 36 weeks.
Study Results
Clinical Responses
Studies M02-403 and M04-691
A statistically significantly greater percentage of the patients treated with adalimumab injection 160/80 mg achieved induction of clinical remission versus placebo at Week 4 regardless of whether the patients were TNF-blocker naïve (Study M02-403) or had lost response or are intolerant to infliximab (Study M04-691) (Table 35 and Table 36, respectively).
The percentage of subjects who achieved clinical remission with adalimumab injection 160/80 mg induction therapy was greater for those receiving corticosteroids versus those who did not.
Table 35 Induction of Clinical Remission and Response in Infliximab Naïve Patients (Study M02-403) (Percent of Patients)
| Response | Placebo N=74 | Adalimumab injection 160/80 mg N=76 | |||
|---|---|---|---|---|---|
| Response | Placebo N=74 | Adalimumab injection 160/80 mg N=76 | |||
| Week 4 | Clinical remission Differencea (95% CI) | 12% | 36%* 23.4 (10.3, 36.4) | ||
Clinical response (CR-100) Differencea (95% CI) | 24% | 49%** 24.4 (9.5, 39.3) | |||
Clinical response (CR-70) Differencea (95% CI) | 34% | 58%** 24.1 (8.6, 39.6) | |||
All p-values are pairwise comparisons of proportions for adalimumab injection versus placebo * p <0.001 ** p <0.01 a. Difference refers to the difference between the proportion (%) of adalimumab injection-treated subjects achieving clinical remission and clinical response compared with the placebo-treated subjects; 95% CI based on normal approximation of the binomial Definition(s): CI=confidence interval; Clinical remission=Crohn’s Disease Activity Index (CDAI) score <150; Clinical response 100 (CR-100) and a clinical response 70 (CR-70)=decreases from baseline in CDAI scores of at least 100 points and at least 70 points, respectively | |||||
Table 36 Induction of Clinical Remission and Response in Infliximab Experienced Patients (Study M04-691) (Percent of Patients)
| Response | Placebo N=166 | Adalimumab injection 160/80 mg N=159 | |||
|---|---|---|---|---|---|
| Week 4 | Clinical remission Differencea (95% CI) | 7% | 21%* 14.2 (6.7, 21.6) | ||
Clinical response (CR-100) Differencea (95% CI) | 25% | 38%** 13.7 (3.7, 23.7) | |||
Clinical response (CR-70) Differencea (95% CI) | 34% | 52%** 17.8 (7.3, 28.4) | |||
p-values are pairwise comparisons of proportions for adalimumab injection versus placebo * p <0.001 ** p <0.01 a. Difference refers to the difference between the proportion (%) of adalimumab injection-treated subjects achieving clinical remission and clinical response compared with the placebo-treated subjects; 95% CI based on normal approximation of the binomial Definition(s): CI=confidence interval; Clinical remission=Crohn’s Disease Activity Index (CDAI) score <150; Clinical response 100 (CR-100) and a clinical response 70 (CR-70)=decreases from baseline in CDAI scores of at least 100 points and at least 70 points, respectively | |||||
Clinical Remission at Week 4 by baseline predictors in infliximab experienced patients is presented in Table 37.
Table 37 Clinical Remission at Week 4 by Baseline Predictors in Infliximab Experienced Patients (Study M04-691)
| Baseline Predictors | Placebo | Adalimumab injection 160/80 mg |
|---|---|---|
| N=166 | N=159 | |
| Corticosteroid User | 3/73 (4.1) | 18/55 (32.7) |
| Corticosteroid Nonuser | 9/93 (9.7) | 16/104 (15.4) |
| Aminosalicylate User | 6/60 (10.0) | 6/45 (13.3) |
| Aminosalicylate Nonuser | 6/106 (5.7) | 28/114 (24.6) |
| CDAI Score | ||
≤300 >300 | 8/81 (9.9) 4/85 (4.7) | 24/75 (32.0) 10/84 (11.9) |
| Definition(s): CDAI=Crohn’s disease activity index | ||
Study M02-404
At Week 4, 58% (499/854) of patients were in clinical response and were assessed in the primary analysis. Of those in clinical response at Week 4, 48% had been previously exposed to other anti-TNF therapy. At Weeks 26 and 56, statistically significantly greater proportions of patients who were in clinical response at Week 4 achieved clinical remission in the adalimumab injection maintenance groups compared to patients in the placebo maintenance group (Table 38).
Table 38 Maintenance of Clinical Remission and Response (Percent of Patients) (Study M02-404)
| Response | Placebo | Adalimumab injection 40 mg eow | Adalimumab injection 40 mg ew | ||||||
|---|---|---|---|---|---|---|---|---|---|
| Response | Placebo | Adalimumab injection 40 mg eow | Adalimumab injection 40 mg ew | ||||||
| N=170 | N=172 | N=157 | |||||||
| N=170 | N=172 | N=157 | |||||||
| Week 26 | Clinical remission Differencea (95% CI) | 17% | 40%* 22.5 (13.2, 31.7) | 47%* 29.4 (19.8, 39.1) | |||||
Clinical response (CR-100) Differencea (95% CI) | 27% | 52%* 25.3 (15.3, 35.3) | 52%* 25.8 (15.5, 36.0) | ||||||
| Clinical response (CR-70) Differencea (95% CI) | 28% | 54%* 25.8 (15.8, 35.9) | 56%* 27.8 (17.5, 38.1) | ||||||
| Week 56 | Clinical remission Differencea (95% CI) | 12% | 36%* 24.3 (15.6, 32.9) | 41%* 29.6 (20.5, 38.7) | |||||
Clinical response (CR-100) Differencea (95% CI) | 17% | 41%* 24.8 (15.6, 34.0) | 48%* 31.3 (21.7, 40.9) | ||||||
Clinical response (CR-70) Differencea (95% CI) | 18% | 43%* 25.4 (16.9, 34.7) | 49%* 31.4 (21.7, 41.1) | ||||||
* p <0.001 for adalimumab injection versus placebo pairwise comparisons of proportions a. Difference refers to the difference between the proportion (%) of adalimumab injection-treated subjects achieving clinical remission and clinical response compared with the placebo-treated subjects; 95% CI based on normal approximation of the binomial Definition(s): eow=every other week; ew=every week; CI=confidence interval; Clinical remission=Crohn’s Disease Activity Index (CDAI) score <150; Clinical response 100 (CR-100) and clinical response 70 (CR-70)=decreases from baseline in CDAI scores of at least 100 points and at least 70 points, respectively | |||||||||
More patients receiving adalimumab injection maintenance therapy were able to achieve remission and discontinue corticosteroids for at least 90 days than those receiving placebo at Week 26 (19% adalimumab injection every other week and 15% adalimumab injection every week versus 3% placebo, p <0.02) and at Week 56 (29% adalimumab injection every other week and 20% adalimumab injection every week versus 5% placebo, p <0.01).
In Study M02-404, 117 patients had at least one draining fistula at Baseline and Screening. Of those, 23 out of 70 in the adalimumab injection group (both regimens) and 6 out of 47 in the placebo group had no draining fistula at the last two evaluations.
Of those in response at Week 4 who attained remission during the study, patients in the adalimumab injection maintenance groups, maintained remission for a significantly longer time than patients in the placebo maintenance group (Figure 4).
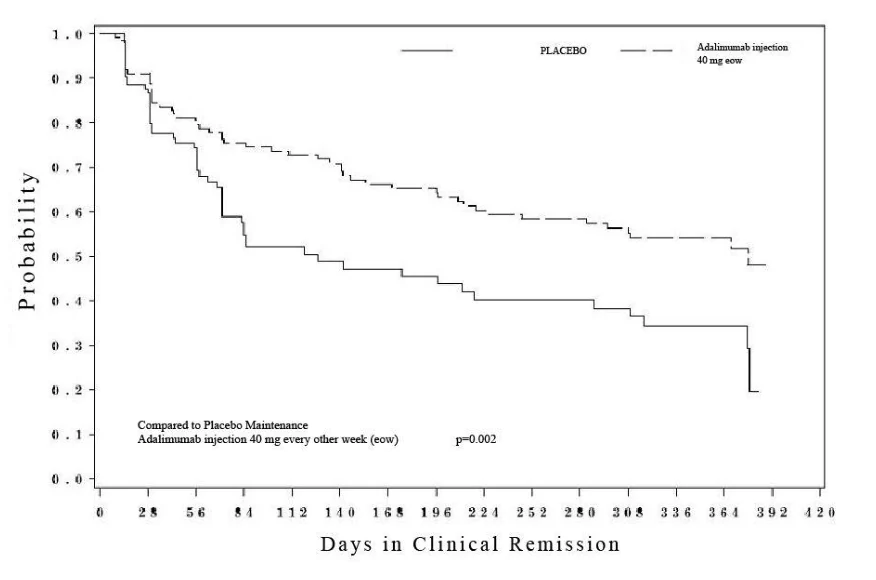
Figure 4. Days in Clinical Remission for Patients Who Had Achieved Clinical Remission (Induction Period) by Week 4 in Study M02-404
Some patients who experience decrease in their response may benefit from an increase in dose to adalimumab injection 40 mg every week. Supportive evidence for a restoration of clinical response as a result of dose escalation was derived from the modified-intent-to treat (mITT) Analysis Set of Study M02-404 in subjects who initially responded but lost response to adalimumab injection 40 mg every other week dosing. In those subjects who responded at Week 4, were in remission at Week 12 but lost remission after Week 12, and were dose escalated to adalimumab injection 40 mg every week (n=14), clinical remission was restored in 71% (10/14) of these subjects, with median time to restored clinical remission of 9 weeks.
Some patients who have not responded by Week 4 (induction period) may benefit from continued maintenance therapy through Week 12. Available data suggest that the clinical response is usually achieved at Week 4 of treatment. Continued therapy should be carefully reconsidered in a patient not responding within this time period.
Symptoms, overall well-being and functioning were assessed using the Inflammatory Bowel Disease Questionnaire (IBDQ). Treatment with adalimumab injection resulted in statistically significant improvements in IBDQ total score which measures bowel symptoms, systemic symptoms, emotional well-being and social functioning, compared with placebo (p <0.001) at Week 4 in Studies M02-403 and M04-691 and Weeks 26 and 56 in Study M02-404.
Study M05-769
An endoscopy study (n=135) assessed rates of mucosal healing in patients with moderate to severe Crohn’s Disease given either adalimumab injection or placebo. After 8 weeks of randomized treatment (Week 12 of study), although the results were not statistically significant (p=0.056), there was a trend towards higher levels of mucosal healing in subjects given adalimumab injection compared with subjects given placebo (mucosal healing in 27.4% (17/62) adalimumab injection vs 13.1% (8/61) given placebo. In this study, the placebo group received open-label adalimumab injection induction therapy.
Ulcerative Colitis
The safety and efficacy of multiple doses of adalimumab injection were assessed in adult patients with moderately to severely active ulcerative colitis (UC) (Mayo score 6 to 12 on a scale of 0 to 12 points, with an endoscopy subscore of 2 to 3 on a scale of 0 to 3) despite concurrent or prior treatment with immunosuppressants such as corticosteroids, azathioprine, or 6-MP in two randomized, double-blind, placebo-controlled studies (M06-826 and M06-827) and an open-label extension study. Both studies M06-826 and M06-827 enrolled TNF-blocker naïve patients, but M06-827 also allowed entry of patients who lost response or were intolerant to TNF-blockers. Forty percent (40%) of patients enrolled in Study M06-827 had previously used another TNF-blocker.
Concomitant stable doses of aminosalicylates, corticosteroids, and/or immunomodulatory agents were permitted. In Studies M06-826 and M06-827, patients were receiving aminosalicylates (69%), corticosteroids (59%) and/or azathioprine or 6-MP (37%) at baseline. In both studies, 92% of patients continued to receive at least one of these medications.
Table 39 summarizes the controlled clinical trials and Table 40 summarizes the open-label clinical trial that were done in patients with ulcerative colitis (UC).
Table 39 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Ulcerative Colitis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender | |||
|---|---|---|---|---|---|---|---|---|
| (n) | (Range) | (% Female) | ||||||
M06-826 (UC I) (ULTRA I) | Randomized, double-blind (Weeks 0 to 8), placebo-controlled, multicenter induction study followed by an open-label extension (Weeks 8 to 52) in anti-TNF naïve subjects | Adalimumab injection 160 mg at Week 0, 80 mg at Week 2, and 40 mg eow starting at Week 4 | 223* | 38 ± 13 (18 to 75) | 38.1 | |||
| Adalimumab injection 80 mg at Week 0 and 40 mg eow starting at Week 2 | 130 | 42 ± 14 (18 to 75) | 40.0 | |||||
Placebo Subcutaneous 52 weeks | 222* | 40 ± 13 (18 to 74) | 37.4 | |||||
M06-827 (UC II) (ULTRA II) | Randomized, double-blind, placebo-controlled, multicenter induction and maintenance study | Adalimumab injection 160 mg at Week 0, 80 mg at Week 2, and 40 mg eow starting at Week 4 | 248 | 40 ± 12 (18 to 72) | 42.7 | |||
Placebo Subcutaneous 52 weeks | 246 | 41 ± 13 (18 to 79) | 38.2 | |||||
Definition(s): ew=every week; eow=every other week * 130 subjects were randomized for the primary efficacy analysis | ||||||||
Table 40 Summary of Open-Label Clinical Trials Supporting Safety and Efficacy in Patients with Ulcerative Colitis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
| (n) | (Range) | (% Female) | |||
| (n) | (Range) | (% Female) | |||
| M10-223 (UC III) | Open-label extension of controlled Studies M06-826 and M06-827 | Patients entering the study from a blinded cohort were assigned to adalimumab injection 40 mg eow; those entering the study from an open-label cohort continued their previous dosing regimen | 498 | 42 ± 13 (19 to 76) | 36.9 |
| of adalimumab injection 40 mg eow or ew. Subcutaneous up to 292 weeks | |||||
| Definition(s): ew=every week; eow=every other week | |||||
Description of Clinical Studies
Induction of clinical remission (defined as Mayo score ≤2 with no individual subscore >1) at Week 8 was evaluated in Study M06-826. In Study M06-826, 390 TNF-blocker naïve patients were randomized to one of three treatment groups for the primary efficacy analysis. The placebo group received placebo at Week 0, 2, 4 and 6. The 160/80 group received 160 mg adalimumab injection at Week 0 and 80 mg at Week 2, and the 80/40 group received 80 mg adalimumab injection at Week 0 and 40 mg at Week 2. After Week 2, patients in both adalimumab injection treatment groups received 40 mg every other week (eow). Clinical remission was assessed at Week 8.
Induction of clinical remission at Week 8, clinical remission at Week 52 and sustained clinical remission (defined as clinical remission at both Weeks 8 and 52) were studied in Study M06-827. In Study M06-827, 518 patients were randomized to receive either adalimumab injection 160 mg at Week 0, 80 mg at Week 2, and 40 mg eow starting at Week 4 through Week 50, or placebo starting at Week 0 and eow through Week 50. Corticosteroid taper was permitted starting at Week 8.
Study Results
Clinical Responses
In both Studies M06-826 and M06-827, a greater proportion of subjects induced with 160/80 mg adalimumab injection achieved clinical remission versus placebo at Week 8 (Table 41). In Study M06-826, there was no statistically significant difference in clinical remission observed between the adalimumab injection 80/40 mg group and the placebo group at Week 8 and no statistically significant difference in clinical response or mucosal healing observed between the adalimumab injection 160/80 mg group and the placebo group at Week 8. Response at Week 8 was achieved by 54.6% (71/130) in the adalimumab injection 160/80 mg group and 44.6% (58/130) in the placebo group with a treatment difference and 95% confidence interval (CI) of 10.0% (-2.1, 22.1). Mucosal healing at Week 8 was achieved by 46.9% (61/130) in the adalimumab injection group and 41.5% (54/130) in the placebo group with a treatment difference and 95% CI of 5.4% (-6.7, 17.4).
In Study M06-827 clinical remission at Week 52 was a co-primary endpoint, achieved by 17.3% (43/248) of the adalimumab injection group and 8.5% (21/246) of the placebo group. Sustained clinical remission (at both Weeks 8 and 52) was achieved by 8.5% (21/248) of the adalimumab injection group and 4.1% (10/246) of the placebo group. Among those treated with adalimumab injection who were in remission at Week 8, 51% (21/41) were in remission at Week 52. In the adalimumab injection group 46.8% (116/248) patients moved to open label escape therapy for lack of response and 54.9% (135/246) patients in the placebo group. During the double-blind period, 5.6% (14/248) in the adalimumab injection group and 7.7% (19/246) in the placebo group withdrew without final evaluation due to non-colitis related reasons (not lack of efficacy or colitis related adverse event). In the adalimumab injection group 79 (31.9%) patients completed the Week 8 and 52 visits and 56 (22.8%) patients in the placebo group.
Response at Week 8 and at Week 52 were achieved in 50.4% (125/248) and 30.2% (75/248) of the adalimumab injection group and 34.6% (85/246) and 18.3% (45/246) in the placebo group respectively with a treatment difference and 95% CI of 15.9% (7.0, 24.2) and 11.9% (4.3, 19.2). Sustained response (at both Weeks 8 and 52) was achieved by 23.8% (59/248) of the adalimumab injection group and 12.2% (30/246) of the placebo group with a treatment difference and 95% CI of 11.6% (4.7, 18.1).
Mucosal healing (endoscopic improvement of the mucosa) at Week 8 and at Week 52 were achieved in 41.1% (102/248) and 25.0% (62/248) in the adalimumab injection group and 31.7% (78/246) and 15.4% (38/246) of the placebo group with a treatment difference and 95% CI of 9.4% (0.8, 17.6) and 9.6% (2.3, 16.4). Sustained mucosal healing (at both Weeks 8 and 52) was achieved by 18.5% (46/248) of the adalimumab injection group and 10.6% (26/246) of the placebo group with a treatment difference and 95% CI of 8.0% (1.6, 14.0).
In the adalimumab injection group, 13.3% (20/150) of the patients who were on corticosteroids at baseline were able to discontinue corticosteroids before Week 52 and achieved remission at Week 52 compared to 5.7% (8/140) in the placebo group.
Table 41 Study M06-826 and M06-827: Summary of Results of Primary and Ranked Co-Primary and Ranked Secondary Endpoints
| Analysisa | Placebo | Adalimumab injection 160/80/40 | Treatment Difference (95% CI) | ||||
|---|---|---|---|---|---|---|---|
| Study M06-826 | N=130 | N=130 | |||||
| Primary Endpoint | |||||||
| Clinical remission at Week 8 | 9.2% | 18.5%* | 9.2 (0.9, 17.6) | ||||
| Study M06-827 | N=246 | N=248 | |||||
| Ranked Co-Primary Endpoints | |||||||
| 9.3% 8.5% | 16.5%* 17.3%* | 7.2 (1.2, 12.9) 8.8 (2.8, 14.5) | ||||
Note: According to the NRI method, all missing remission values were considered to be non-remission. Subjects who switched to OL adalimumab injection were considered to be non-remitters at and after the time of the switch. Clinical remission per Mayo score: Mayo score ≥2 with no individual subscore >1 Mayo score consists of four subscores (stool frequency [SFS], rectal bleeding [RBS], findings of endoscopy, and physician’s global assessment). Mayo scores range from 0-12. * p<0.05 for adalimumab injection vs. placebo pairwise comparison of proportions | |||||||
In the subgroup of patients in Study M06-827 with prior TNF-blocker use, the treatment difference for induction of clinical remission was lower than that seen in the whole study population, and the treatment differences for sustained clinical remission and clinical remission at Week 52 appeared to be similar to those seen in the whole study population.
Hidradenitis Suppurativa
The safety and efficacy of adalimumab injection were assessed in two randomized, double-blind, placebo-controlled studies in adult patients with moderate to severe hidradenitis suppurativa (HS) who were intolerant, had a contraindication or an inadequate response to systemic antibiotic therapy. In both studies, patients had Hurley Stage II or III disease with at least 3 abscesses or inflammatory nodules. Table 42 summarizes the clinical trials in patients with moderate to severe hidradenitis suppurativa.
Table 42 Summary of Clinical Trials Evaluating Safety and Efficacy in Patients with Hidradenitis Suppurativa
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
| (n) | (Range) | (% Female) | |||
| (n) | (Range) | (% Female) | |||
| M11-313 (PIONEER I) | Randomized, double-blind, placebo-controlled, 2-period | Period A - 12 weeks Adalimumab injection 160 mg at Week 0, 80 mg at Week 2, then 40 mg every week from Week 4 to Week 11; Placebo Period B - 24 weeks Adalimumab injection 40 mg every week; Adalimumab injection 40 mg every other week; Placebo Subcutaneous 36 weeks | 307 | 37.0 (18 to 67) | 63.8 |
M11-810 (PIONEER II) | Randomized, double-blind, placebo-controlled, 2-period | Period A - 12 weeks Adalimumab injection 160 mg at Week 0, 80 mg at Week 2, then 40 mg every week from Week 4 to Week 11; Placebo Period B - 24 weeks Adalimumab injection 40 mg every week; Adalimumab injection 40 mg every other week; | 326 | 35.5 (18 to 69) | 67.8 |
Placebo Subcutaneous 36 weeks | |||||
Description of Clinical Studies
Both studies consisted of an initial 12-week double-blind treatment period (Period A), and a subsequent 24-week double-blind treatment period (Period B). In Period A, patients received placebo or adalimumab injection at an initial dose of 160 mg at Week 0, 80 mg at Week 2, and 40 mg every week starting at Week 4 to Week 11. After 12 weeks of therapy, patients who had received adalimumab injection in Period A were re-randomized in Period B to 1 of 3 treatment groups (adalimumab injection 40 mg every week, adalimumab injection 40 mg every other week, or placebo from Week 12 to Week 35). In Period B, patients who had been randomized to placebo in Period A were assigned to receive adalimumab injection 40 mg every week (M11-313) or placebo (M11-810) in a blinded fashion. In both studies, the randomization in Period A was to be stratified by baseline Hurley Stage (II versus III). A subject's Hurley Stage was determined by the worst Hurley Stage across all affected anatomic regions. Baseline concomitant antibiotic use (yes versus no) was an additional randomization factor in Study M11-810.
Both studies evaluated Hidradenitis Suppurativa Clinical Response (HiSCR) at Week 12 as the primary endpoint. Reduction of inflammatory lesions and prevention of worsening of abscesses and draining fistulas was assessed using HiSCR which was defined as achieving at least a 50% reduction from baseline in AN [total abscess and inflammatory nodule] count plus no increase in abscess count and no increase in draining fistula count relative to baseline. Reduction in HS-related skin pain was assessed using a Numeric Rating Scale in patients who entered the study with an initial baseline score of 3 or greater on a 11-point scale.
The majority of patients were female, obese (≥90 kg, BMI ≥30), current smokers, and had HS disease duration of over 9 years; the patients had a mean modified Sartorius Score of 131.6, AN count of 12.8, and draining fistula count of 3.8.
Patients participating in Studies M11-313 and M11-810 were eligible to enroll into an open-label extension study (Study M12-555) in which adalimumab injection 40 mg was administered every week. Study M12-555 aimed to determine the long-term safety, tolerability and efficacy of adalimumab injection in subjects with moderate to severe HS for at least 60 weeks.
Throughout all 3 studies, patients used topical antiseptic wash daily.
Study Results
Clinical Responses
Studies M11-313 and M11-810
In Period A of Studies M11-313 and M11-810, 40 mg of adalimumab injection treatment every week resulted in statistically significant greater proportion of patients achieving HiSCR at Week 12 in subjects with moderate to severe HS compared with placebo. Results are shown in Table 43.
Table 43 Clinical Response at 12 Weeks, M11-313 and M11-810
| Endpoint | M11-313 (PIONEER I) | M11-810 (PIONEER II) | |||||||||||
| Placebo | Adalimumab injection 40 mg weekly | Placebo | Adalimumab injection 40 mg weekly | ||||||||||
Hidradenitis Suppurativa Clinical Response (HiSCR) | N=154 40 (26.0%) | N=153 64 (41.8%) | N=163 45 (27.6%) | N=163 96 (58.9%) | |||||||||
| Difference (95% CI)a | 15.9% (5.3%, 26.5%) | 31.5% (20.7, 42.2%) | |||||||||||
| P-valueb | 0.003 | <0.001 | |||||||||||
a. 95% CI for stratum-adjusted difference was calculated according to the extended Mantel-Haenszel statistic for the comparison of two treatment groups, adjusting for baseline Hurley Stage (II/III) in M11-313 and adjusting for baseline Hurley Stage (II/III) and baseline antibiotic use (Yes/No) in M11-810. b. P-value was calculated from the Cochran-Mantel-Haenszel test adjusting for baseline Hurley Stage (II/III) in M11-313, and adjusting for baseline Hurley Stage (II/III) and baseline antibiotic use (Yes/No) in M11-810. | |||||||||||||
At Week 12, a significantly higher proportion of patients treated with adalimumab injection in Study M11-810 experienced at least a 30% decrease in HS-related skin pain versus placebo (45.7% vs 20.7%, P <0.001), whereas the difference was not significant in Study M11-313 (27.9% vs 24.8%, P=0.628). During the initial 12 weeks of treatment, 13.7% of patients treated with adalimumab injection experienced flare compared to 35.7% in the placebo group in Study M11-313. The corresponding observed percentage was 11.0% and 35.0% for the adalimumab injection and placebo group, respectively, in Study M11-810.
Among patients who were randomized to adalimumab injection in Period A, achieved HiSCR at Week 12, and re-randomized to adalimumab injection every week (N=52), adalimumab injection every other week (N=52) and placebo (N=53), 24 (46.2%), 22 (42.3%), and 32 (60.4%) discontinued prior to Week 36, respectively; 17 (32.7%), 20 (38.5%), and 27 (50.9%) discontinued primarily due to experiencing protocol specified loss of response.
In patients with at least a partial response (≥25% improvement in AN count) to adalimumab injection 40 mg weekly at Week 12, the proportion of patients achieving HiSCR at Week 24 was 57.1% in adalimumab injection 40 mg weekly, 51.4% in adalimumab injection 40 mg every other week and 32.9% in the placebo group. The corresponding proportion at Week 36 was 55.7% in adalimumab injection 40 mg weekly, 40.0% in adalimumab injection 40 mg every other week and 30.1% in the placebo group.
Plaque Psoriasis
The safety and efficacy of adalimumab injection were assessed in over 1,600 patients 18 years of age or older with moderate to severe chronic plaque psoriasis who were candidates for systemic therapy or phototherapy in randomized, double-blind, well-controlled studies.
Table 44 summarizes the controlled clinical trials that were done in patients with moderate to severe plaque psoriasis.
Table 44 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Psoriasis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender | |||||||
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender | |||||||
| (n) | (Range) | (% Female) | ||||||||||
| (n) | (Range) | (% Female) | ||||||||||
| (n) | (Range) | (% Female) | ||||||||||
| M03-656 (Ps I) | Period A: Double-blind, placebo-controlled treatment period in patients with moderate to severe chronic plaque psoriasis (PASI ≥12, BSA ≥10%); patients were randomly assigned (2:1) to receive adalimumab injection or placebo Period B: Open-label treatment period; all patients who achieved a ≥PASI 75 response at Week 16 received adalimumab injection Period C: Double-blind, placebo-controlled treatment period; patients who maintained a ≥PASI 75 response at Week 33 and were originally randomized to active therapy in Period A were rerandomized (1:1) to receive adalimumab injection or placebo | Initial Dose Adalimumab injection 80 mg | ||||||||||
Period A - 16 weeks Adalimumab injection 40 mg eow Placebo | 814 398 | 44.1 ± 13.2 45.4 ± 13.4 | 32.9 35.4 | |||||||||
Period B - 17 weeks Adalimumab injection 40 mg eow | 606 | 43.9 ± 13.2 | 30.7 | |||||||||
Period C - 19 weeks Adalimumab injection 40 mg eow Placebo | 250 240 | 44.3 ± 13.0 43.4 ± 13.2 | 29.6 25.4 | |||||||||
Subcutaneous 52 weeks | ||||||||||||
M04-716 (Ps II) | Adalimumab injection 80 mg followed by 40 mg eow | 108 | 42.9 ± 12.6 | 35.2 | ||||||||
| Placebo | 53 | 40.7 ± 11.4 | 34.0 | |||||||||
methotrexate capsules (7.5 to 25.0 mg) | 110 | 41.6 ± 12.0 | 33.6 | |||||||||
Subcutaneous and oral 16 weeks | ||||||||||||
M02-528 (Ps III) | Randomized, double-blind, placebo-controlled, multicenter, dose-ranging study in patients with moderate to severe plaque psoriasis (BSA ≥5%) and inadequate response to topical therapy | Adalimumab injection 80 mg followed by 40 mg eow | 45 | 45.8 ± 11.6 | 28.9 | |||||||
| Adalimumab injection 80 mg followed by 40 mg ew | 50 | 43.8 ± 13.3 | 34.0 | |||||||||
| Placebo | 52 | 43.3 ± 13.1 | 34.6 | |||||||||
Subcutaneous 12 weeks | ||||||||||||
| M13-674 (Ps IV) | Period A: Double-blind, placebo-controlled treatment period during which patients with moderate to severe nail psoriasis (PGA and PGA-F of at least moderate disease severity; a target-fingernail mNAPSI ≥8 together with either BSA ≥10% or a total mNAPSI score of ≥20 with ≥5% BSA involvement) were randomized in a 1:1 ratio to receive | Period A - 26 weeks Adalimumab injection 80 mg followed by 40 mg eow Placebo Period B - 26 weeks adalimumab injection 40 mg eow Subcutaneous 52 weeks | 217 | 46.7 ± 12.0 | 15.7 | |||||||
adalimumab injection or placebo Period B: Open-label treatment period; all patients received adalimumab injection | ||||||||||||
| Definition(s): ew=every week; eow=every other week; MTX=methotrexate; PASI=Psoriasis Area and Severity Index; BSA=body surface area; PGA=Physician’s Global Assessment; PGA-F: Physician’s Global Assessment of Fingernail Psoriasis; mNAPSI=Modified Nail Psoriasis Severity Index | ||||||||||||
Across all treatment groups of Study M03-656, the mean baseline Psoriasis Area and Severity Index (PASI) score was 18.9 and the baseline physician’s global assessment (PGA) score ranged from “moderate” (52.6%) to “severe” (41.3%) to “very severe” (6.1%).
Across all treatment groups of Study M04-716, the mean baseline PASI score was 19.7 and the baseline PGA score ranged from “mild” (0.4%) to “moderate” (47.8%) to “severe” (45.6%) to “very severe” (6.3%).
Patients participating in all Phase 2 and Phase 3 psoriasis studies were eligible to enroll into an open-label extension trial, where adalimumab injection was given for at least an additional 108 weeks. 1,468 patients received at least one dose of adalimumab injection during the open-label trial. 1,018/1,468 (69%) patients received adalimumab injection for a minimum of 108 weeks. Patients from Study M03-656 who enrolled into the open-label trial may have received up to 160 weeks of continuous adalimumab injection exposure in the first portion of the extension. 183/233 (79%) eligible patients from Study M03-656 completed 160 weeks from the first dose of adalimumab injection in M03-656 to the end of the first portion of the extension trial.
Study Results
Clinical Response
In Studies M03-656, M04-716 and M02-528, the primary endpoint was the proportion of patients who achieved a reduction in PASI score of at least 75% (PASI 75) from baseline at Week 16 for Studies M03-656 and M04-716 and Week 12 for Study M02-528. Other evaluated outcomes in Studies M03-656, M04-716 and M02-528 included the PGA and other PASI measures.
Study M03-656 had an additional primary endpoint of loss of adequate response after Week 33 and on or before Week 52. Loss of adequate response is defined as a PASI score after Week 33 and on or before Week 52 that resulted in a <PASI 50 response relative to baseline with a minimum of a 6-point increase in PASI score relative to Week 33.
In Study M03-656, response to adalimumab injection was rapid, with significantly greater improvements compared to placebo in mean percentage PASI, PASI 75/90 response rates, and PGA clear or minimal scores by Week 4, the first study visit (all p <0.001 vs. placebo).
In Studies M03-656 and M04-716, more patients randomized to adalimumab injection than to placebo achieved at least a 75% reduction from baseline of PASI score at Week 16 (see Table 45 and Table 46). Other relevant clinical parameters, including PASI 90, PASI 100 (corresponding to a complete clearance of psoriasis skin signs) and PGA of “clear or minimal,” were also improved over placebo.
In Study M04-716, superior results were achieved for PASI 75, PASI 90, PASI 100 and PGA of “clear or minimal” in patients randomized to the adalimumab injection treatment group versus those randomized to receive methotrexate.
Table 45 Psoriasis Study M03-656 Efficacy Results at Week 16 (Percent of Patients)
| Response | Placebo | Adalimumab injection 40 mg eow | ||
| N=398 | N=814 | |||
| ≥PASI 75 | 6.5% | 70.9%a | ||
| ≥PASI 90 | 1.8% | 45.0%a | ||
| PASI 100 | 0.8% | 20.0%a | ||
| PGA: Clear/minimal | 4.3% | 62.2%a | ||
a. p <0.001 for adalimumab injection versus placebo Definition(s): eow=every other week; PASI=Psoriasis Area Severity index; PGA=physician’s global assessment | ||||
Table 46. Psoriasis Study M04-716 Efficacy Results at Week 16 (Percent of Patients)
| Response | Placebo | MTX | Adalimumab injection 40 mg eow | |||
|---|---|---|---|---|---|---|
| N=53 | N=110 | N=108 | ||||
| ≥PASI 75 | 18.9% | 35.5% | 79.6%a,b | |||
| ≥PASI 90 | 11.3% | 13.6% | 51.9%a,b | |||
| PASI 100 | 1.9% | 7.3% | 16.7%c,d | |||
| PGA: Clear/minimal | 11.3% | 30.0% | 73.1%a,b | |||
a. p <0.001 for adalimumab injection versus placebo b. p <0.001 for adalimumab injection versus MTX c. p <0.01 for adalimumab injection versus placebo d. p <0.05 for adalimumab injection versus MTX Definition(s): MTX=methotrexate; eow=every other week; PASI=Psoriasis Area Severity index; PGA=physician’s global assessment | ||||||
PASI 75, PASI 90 and PASI 100 Responses from Week 0 to Week 24 for Study M03-656 are presented in Figure 5.
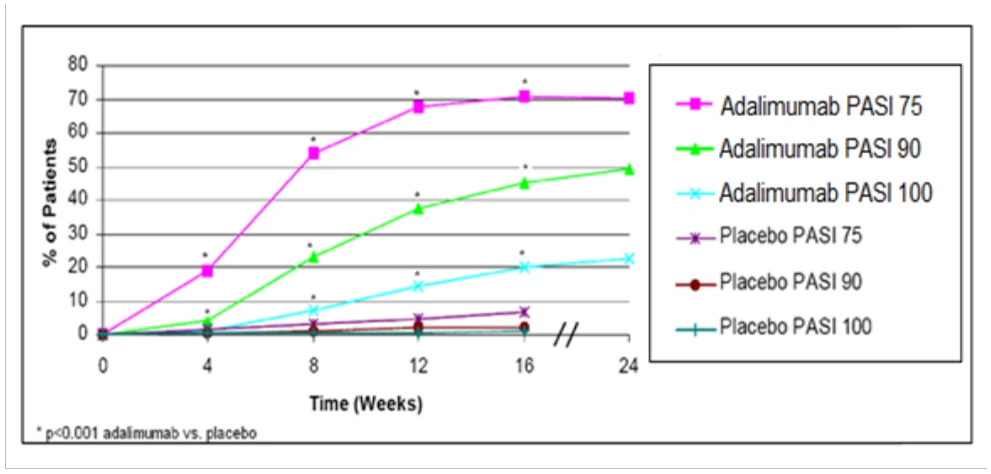
Figure 5. Psoriasis Study M03-656 Response Rate from Week 0 to Week 24
Results from Study M02-528 supported the efficacy demonstrated in Studies M03-656 and M04-716.
In Study M03-656, patients who were PASI 75 responders and were re-randomized to continue adalimumab injection therapy at Week 33 were less likely to experience a loss of adequate response on or before Week 52 than the PASI 75 responders who were re-randomized to placebo at Week 33 (4.9% versus 28.4%, p <0.001).
A total of 233 PASI 75 responders at Week 16 and Week 33 received continuous adalimumab injection therapy for 52 weeks in Psoriasis Study M03-656, and continued adalimumab injection in the open-label extension trial. The proportion of patients with full skin clearance (PASI 100) was generally maintained through Week 108 [31.8% at OLE entry (n=74/233); 30.1% at Week 108 (n=69/229 (total of 160 weeks)].
A total of 94 patients were randomized to adalimumab injection therapy in Psoriasis Study M04-716, and continued adalimumab injection in the open label extension trial. The proportion of patients with PASI 75 after an additional 108 weeks of open-label therapy was 58.1% (n=54/93) (total of 124 weeks).
A total of 347 stable responders participated in a withdrawal and retreatment evaluation in an open-label extension study. Median time to relapse (decline to PGA “moderate” or worse) was approximately 5 months [95% C.I. (127, 146 days)]. None of these patients experienced rebound during the withdrawal period. A total of 76.5% (218/285) of patients who entered the retreatment period had a response of PGA “clear” or “minimal” after 16 weeks of retreatment, 69.1% (123/178) for patients who relapsed and 88.8% (95/107) for patients who did not relapse during the withdrawal period.
In the open-label extension study, 349/1,256 (27.8%) patients dose escalated from 40 mg every other week to 40 mg weekly due to a PASI response below 50% and were evaluated 12 weeks after dose escalation, and 93/349 (26.6%) patients achieved PASI 75 response.
There were no clinical trials conducted to evaluate the efficacy and safety of adalimumab injection in psoriatic arthritis patients with both active arthritis and moderate to severe psoriasis.
Study M13-674 evaluated the proportion of patients who achieved “clear” or “minimal” nail psoriasis with at least a 2-grade improvement on the 5-point Physician’s Global Assessment of Fingernail Psoriasis (PGA-F) scale and at least a 75% improvement in Modified Nail Psoriasis Severity Index (mNAPSI 75) at Week 26. At Week 26, a statistically significantly higher proportion of patients in the adalimumab injection group achieved a PGA-F and mNAPSI 75 response compared with placebo (see Table 47).
Table 47. Nail Psoriasis Study M13-674 Efficacy Results at 26 Weeks
| Response | Placebo N=108 | Adalimumab injection 40 mg eow N=109 | ||
| PGA-F clear/minimal and ≥2-grade improvement | 6.9% | 48.9%a,b | ||
| ≥mNAPSI 75 | 3.4% | 46.6%a,b | ||
a. p <0.001 for adalimumab injection versus placebo b. Across all the strata, P value was calculated according to the Cochran-Mantel-Haenszel test adjusted for strata. If zero frequency occurred, strata were dropped and P value was calculated based on Chi-square test (or adjusted Chi-square test based on Campbell (2007) if expected count <5 in any cell). | ||||
Quality of Life
Patient Reported Outcomes (PRO) were evaluated by several measures. Quality of Life was assessed using the disease-specific Dermatology Life Quality Index (DLQI) in Study M03-656 and Study M04-716.
In Study M03-656, patients receiving adalimumab injection demonstrated clinically meaningful improvement in the DLQI total score, disease severity, pain, and pruritus compared to the placebo group at both Weeks 4 and 16. The DLQI result was maintained at Week 52.
In Study M04-716, patients receiving adalimumab injection demonstrated clinically meaningful improvement in the DLQI total score, disease severity, and pruritus compared to the placebo and methotrexate groups at Week 16, and clinically meaningful improvement in pain compared to the placebo group at Week 16.
The Short Form Health Survey (SF-36) was used to assess general health-related quality of life in Study M03-656. The adalimumab injection-treated patients had significantly greater improvement in the SF-36 Physical Component Summary (PCS) and Mental Component Summary (MCS) scores.
Uveitis
The safety and efficacy of adalimumab injection were assessed in adult patients with non-infectious intermediate, posterior, and panuveitis (also known as “non-infectious uveitis affecting the posterior segment”), excluding patients with isolated anterior uveitis, in two randomized, double-masked, placebo-controlled studies (M10-877 and M10-880) and an ongoing open-label extension study (M11-327). Patients received placebo or adalimumab injection at an initial dose of 80 mg followed by 40 mg every other week starting one week after the initial dose. Concomitant stable doses of non-biologic immunosuppressants were permitted.
Table 48 summarizes the controlled clinical trials done in patients with uveitis.
Table 48 Summary of Controlled Clinical Trials Supporting Safety and Efficacy in Patients with Uveitis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
| (n) | (Range) | (% Female) | |||
M10-877 (VISUAL I) | Randomized, double-masked, placebo-controlled, multicenter study | Adalimumab injection 80 mg loading dose, followed by 40 mg given eow starting at Week 1 | 110 | 42.7± 15.6 (18 to 81) | 53.6 |
| Placebo | 107 | 42.6± 14.2 (18 to 79) | 60.7 | ||
Subcutaneous Up to 80 weeks | |||||
M10-880 (VISUAL II) | Randomized, double-masked, placebo-controlled, multicenter study | Adalimumab injection 80 mg loading dose, followed by 40 mg given eow SC starting at Week 1 | 115 | 42.9 ±12.9 (18 to 75) | 57.4 |
| Placebo | 111 | 42.2±13.98 (20 to 29) | 64.9 | ||
Subcutaneous Up to 80 weeks | |||||
M11-327 (VISUAL III) | Open-label extension of controlled Studies M10-877 and M10-880 for patients who had either discontinued from the lead-in studies for having met “treatment failure” criteria (active uveitis subgroup) or had completed the lead-in studies without treatment failure (inactive uveitis subgroup) | Adalimumab injection 40 mg eow | 424 | 43.4 ± 14.1 (19.0 to 81.0) | 58.7 |
Subcutaneous Up to 362 weeks | |||||
| Definition(s): eow=every other week; SC=subcutaneous | |||||
Description of Clinical Studies
The primary efficacy endpoint in both controlled studies was “time to treatment failure”. Treatment failure was defined by a multi-component measurement assessing the loss of disease control based on inflammatory chorioretinal and/or inflammatory retinal vascular lesions, anterior chamber (AC) cell grade, vitreous haze (VH) grade and best corrected visual acuity (BCVA).
Study M10-877 evaluated 217 patients with active uveitis despite treatment with corticosteroids (oral prednisone at a dose of 10 to 60 mg/day). All patients received a standardized dose of prednisone 60 mg/day at study entry followed by a mandatory taper schedule, with complete corticosteroid discontinuation by Week 15.
Study M10-880 evaluated 226 patients with inactive uveitis requiring chronic corticosteroid treatment (oral prednisone 10 to 35 mg/day) at baseline to control their disease. Patients subsequently underwent a mandatory taper schedule, with complete corticosteroid discontinuation by Week 19.
Study M11-327 evaluated the long-term safety and efficacy of adalimumab injection 40 mg every other week in the treatment of uveitis, during which corticosteroid/immunosuppressant treatments could be initiated, maintained, escalated, tapered, or discontinued as needed.
Study Results
Clinical Responses
Results from both studies demonstrated statistically significant reduction of the risk of treatment failure over the course of the study in patients treated with adalimumab injection versus patients receiving placebo (Table 49, Figure 6, Figure 7).
Table 49 Time to Treatment Failure in Uveitis Studies
Analysis Treatment | N | Failure N (%) | Median Time to Failure (Weeks/Months) | HRa | CI 95% for HRa | P valueb | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Time to Treatment Failure at or after Week 6 in Study M10-877 | ||||||||||||||||
| Primary analysis (ITT) | ||||||||||||||||
| Placebo | 107 | 84(78.5) | 13.0/3.0 | - | - | - | ||||||||||
| adalimumab injection | 110 | 60 (54.5) | 24.4/5.6 | 0.50b | 0.36, 0.70b | <0.001 | ||||||||||
| Time to Treatment Failure At or After Week 2 in Study M10-880 | ||||||||||||||||
| Primary analysis (ITT) | ||||||||||||||||
| Placebo | 111 | 61 (55.0) | 36.1/8.3 | - | - | - | ||||||||||
| adalimumab injection | 115 | 45 (39.1) | NEc | 0.50b | 0.39, 0.84b | 0.004 | ||||||||||
Note: Treatment failure at or after Week 6 (Study M10-877), or at or after Week 2 (Study M10-880), was counted as event. Drop outs due to reasons other than treatment failure were censored at the time of dropping out. a. HR of adalimumab injection vs placebo from proportional hazards regression with treatment as factor. b. 2-sided P Value from log rank test. c. NE=not estimable. Fewer than half of at-risk subjects had an event. | ||||||||||||||||
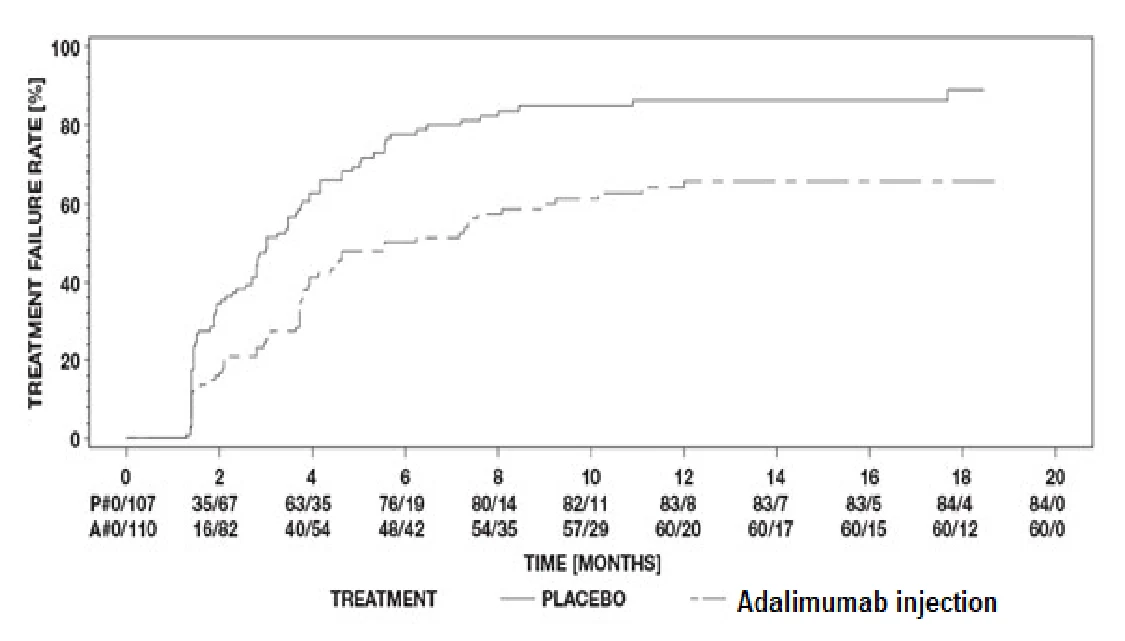
Note: P#=Placebo (Number of Events/Number at Risk); A#= adalimumab injection (Number of Events/Number at Risk)
Figure 6. Kaplan-Meier Curves Summarizing Time to Treatment Failure on-or-after Week 6 (Study M10-877)
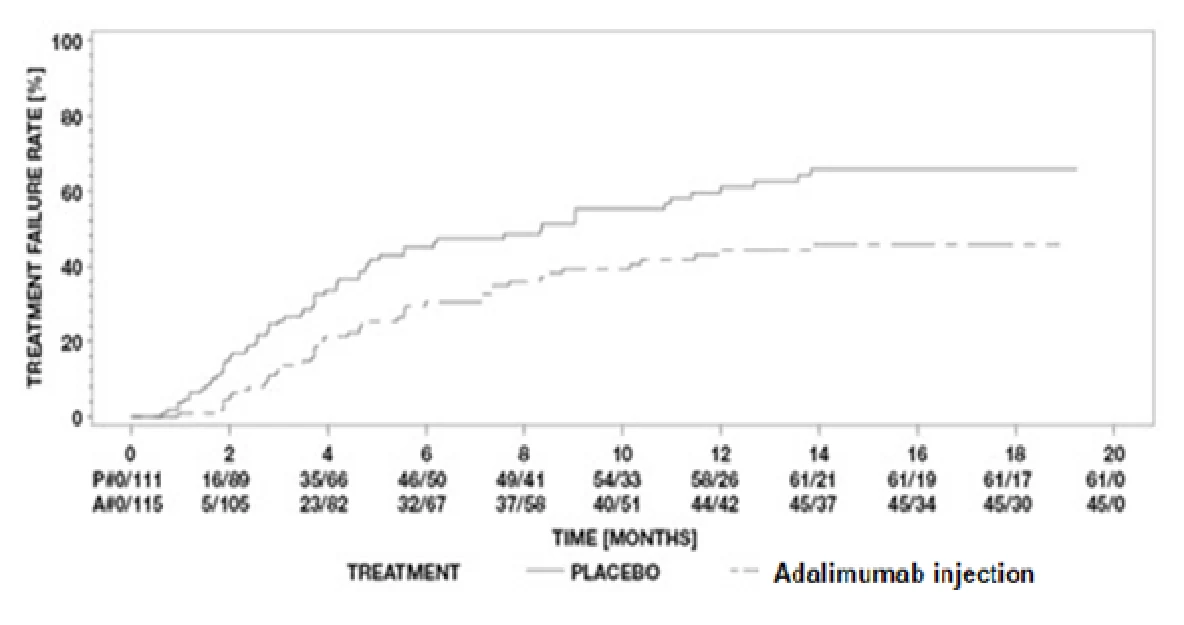
Note: P#=Placebo (Number of Events/Number at Risk); A#= adalimumab injection (Number of Events/Number at Risk)
Figure 7. Kaplan-Meier Curves Summarizing Time to Treatment Failure on-or-after Week 2 (Study M10-80)
In both studies, all components of the primary endpoint contributed cumulatively to the overall difference between adalimumab injection and placebo groups.
Pediatric
Polyarticular Juvenile Idiopathic Arthritis
The safety and efficacy of adalimumab injection was assessed in two studies (Studies DE038 and M10-444) in children with active polyarticular or polyarticular course juvenile idiopathic arthritis (JIA), who had a variety of JIA onset types (most frequently rheumatoid-factor negative or positive polyarthritis and extended oligoarthritis).
Table 50 summarizes the clinical trials that were done in patients with polyarticular JIA.
Table 50 Summary of Clinical Trial Evaluating Safety and Efficacy in Patients with Polyarticular Juvenile Idiopathic Arthritis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) (Years) | Gender (% Female) | ||||
|---|---|---|---|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean Age (Range) (Years) | Gender (% Female) | ||||
| DE038 (JIA I) | Multicenter, double-blind, randomized, placebo-controlled, open-label extension | OL LI Phase 24 mg adalimumab/m2 BSA (up to a maximum of 40 mg total body dose) subcutaneous eow | 171 | 11.3 ± 3.53 (4 to 17) | 78.9% | ||||
DB Phase 24 mg adalimumab/m2 BSA (up to a maximum of 40 mg total body dose) subcutaneous eow or Placebo subcutaneous eow | 133 | 11.6 ± 3.61 (4 to 17) | 77.4% | ||||||
OLE BSA Phase 24 mg adalimumab injection/m2 BSA (up to a maximum of 40 mg total body dose) subcutaneous eow | 128 | 12.0 ± 3.59 (4 to 18) | 76.6% | ||||||
OLE FD Phase 20 mg adalimumab injection subcutaneous eow, <30 kg body weight or 40 mg adalimumab injection subcutaneous eow, ≥30 kg body weight | 106 | 13.7 ± 3.82 (6 to 20) | 73.6% | ||||||
M10-444 (JIA II) | Multicenter, open- label | 24 mg adalimumab injection/m2 BSA (up to a maximum of 20 mg total body dose) subcutaneous eow | 32 | 3.04 ± 0.723 (2.0 to 4.6) | 87.5% | ||||
| Definition(s): BSA=body surface area; DB=double blind; eow=every other week; OL BSA=open-label body surface area; OL FD=open-label fixed dose; OL LI=open-label lead in; SC=subcutaneous. | |||||||||
Study DE038
The safety and efficacy of adalimumab injection were assessed in a multicentre, randomized, double-blind, parallel-group study in 171 pediatric patients (4 to 17 years old at the time of enrollment) with moderate or severe polyarticular juvenile idiopathic arthritis (JIA). In the open-label lead in phase (OL LI) patients were stratified into two groups, MTX (methotrexate)-treated or non-MTX-treated. Patients who were in the non-MTX stratum were either naïve to or had been withdrawn from MTX at least two weeks prior to study drug administration. Patients remained on stable doses of NSAIDs and or prednisone (≤0.2 mg/kg/day or 10 mg/day maximum). In the OL LI phase all patients received 24 mg/m2 up to a maximum of 40 mg adalimumab injection every other week for 16 weeks. The distribution of patients by age and minimum, median and maximum dose received during the OL LI phase is presented in Table 51.
Table 51 Distribution of Patients by Age and Adalimumab injection Dose Received During the OL LI phase
| Age Group | Number of Patients at Baseline n (%) | Minimum, Median and Maximum Dose |
|---|---|---|
| 4 to 7 years | 31 (18.1) | 10, 20 and 25 mg |
| 8 to 12 years | 71 (41.5) | 20, 25 and 40 mg |
| 13 to 17 years | 69 (40.4) | 25, 40 and 40 mg |
Patients demonstrating a Pediatric ACR 30 response at Week 16 were eligible to be randomized into the double blind (DB) phase and received either adalimumab injection 24 mg/m2 up to a maximum of 40 mg, or placebo every other week for an additional 32 weeks or until disease flare. Disease flare criteria were defined as a worsening of ≥30% from baseline in ≥3 of 6 Pediatric ACR core criteria, ≥2 active joints, and improvement of >30% in no more than 1 of the 6 criteria.
After 32 weeks or at disease flare, patients were eligible to enroll into the open label extension phase.
The primary efficacy variable was the proportion of patients in the non-MTX stratum who experienced disease flare in the double-blind phase. Key secondary endpoints were analysis and comparison of disease flare at Week 48 including the proportion of patients with disease flare in those treated with MTX, time to onset (from double blind Baseline) of flare for patients in the non-MTX stratum, and time to onset (from double blind Baseline) of flare for patients treated with MTX. Subjects were clinically assessed at baseline, and for clinical response to adalimumab injection at Weeks 2, 4 and then every 4 weeks up to Week 48 or at early termination and throughout the OLE phases.
Study M10-444
The safety and efficacy of adalimumab injection was assessed in an open-label, multicenter study in 32 children (2 to <4 years old or aged 4 and above weighing <15 kg) with moderately to severely active polyarticular JIA. The primary objective of the study was the evaluation of safety. The patients received 24 mg/m2 body surface area (BSA) of adalimumab injection up to a maximum of 20 mg every other week as a single dose via SC injection for at least 24 weeks up to a maximum of 120 weeks duration. During the study, most subjects used concomitant MTX, with fewer reporting use of corticosteroids or NSAIDs.
Study Results
Table 52 Major Efficacy Results in the JIA Study (DE038)
| Stratum | MTX | Without MTX | |||||||||||||||
| Phase | |||||||||||||||||
| OL-LI 16 weeks | |||||||||||||||||
| Ped ACR 30 response* | 94.1% (80/85) | 74.4% (64/86) | |||||||||||||||
| (n/N) | N=85* | N=86* | |||||||||||||||
| Double Blind | Adalimumab injection | Placebo | Adalimumab injection | Placebo | |||||||||||||
| (n=38) | (n=37) | (n=30) | (n=28) | ||||||||||||||
| Disease flares at the end of 32 weeks (n/N) | 36.8% (14/38) | 64.9% (24/37) | 43.3% (13/30) | 71.4% (20/28)a | |||||||||||||
| Median time to disease flare | >32 weeks | 20 weeks | >32 weeks | 14 weeks | |||||||||||||
a. p=0.031 * N and PedACR30 response rates are from the Open-Label Lead-In phase prior to the randomization to the Double-Blind phase. | |||||||||||||||||
Twelve patients were treated for 6 years or longer.
The percentage of patients achieving PedACR30 responses were higher (94% vs. 74%) and, fewer patients developed antibodies (5.9% vs. 25.6%) when treated with the combination of adalimumab injection and MTX compared to adalimumab injection monotherapy. Therefore, adalimumab injection is recommended for use in combination with methotrexate, and for use as monotherapy only in patients for whom methotrexate use is not appropriate.
Adolescent Hidradenitis Suppurativa (HS)
No clinical trials were conducted in adolescent patients with HS. Efficacy of adalimumab for the treatment of adolescent patients with HS (12 to 17 years of age weighing ≥30 kg) is predicted using pharmacokinetic/pharmacodynamic (PK/PD) modeling and simulations based on demonstrated efficacy and exposure-response relationship in adult HS patients (see 14.5 Clinical Trials– Reference Biologic Drug, Adult, Hidradenitis Suppurativa).
The disease course, pathophysiology and drug effects in adolescents are assumed to be similar to adults at the same exposure levels. Safety of the recommended adalimumab dose in adolescent HS population is based on cross-indication safety profile of adalimumab in both adults and pediatric patients at similar or higher exposures.
Study Results
Not applicable.
Pediatric Uveitis
The safety and efficacy of adalimumab injection were assessed in a randomized, double-masked, controlled study of 90 pediatric patients from 2 to <18 years of age with active JIA-associated noninfectious anterior uveitis who were refractory to at least 12 weeks of methotrexate treatment. Participants were randomized applying a ratio of 2:1 (adalimumab injection: placebo) stratified by centre. Patients received either placebo or 20 mg adalimumab injection (if <30 kg) or 40 mg adalimumab injection (if ≥30 kg) every other week in combination with their baseline dose of methotrexate for up to 18 months. Concomitant stable dosages of systemic (≤0.2 mg/kg/day of prednisolone equivalent) and topical corticosteroids (maximum 6 drops/day) were permitted at study entry followed by a mandatory reduction in topical corticosteroids (maximum 2 drops/day) within 3 months.
Table 53 summarizes the controlled clinical trial done in pediatric patients with uveitis.
Table 53 Summary of Controlled Clinical Trial Supporting Safety and Efficacy in Pediatric Patients with Uveitis
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
|---|---|---|---|---|---|
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects | Mean Age | Gender |
| (n) | (Range) | (% Female) | |||
| (n) | (Range) | (% Female) | |||
| SYCAMORE | Randomized, double-masked, placebo-controlled, | adalimumab injection fixed-dose of 20 mg (if BW <30 kg at Baseline) or 40 mg (if BW ≥30 kg at Baseline) | 60 | 9.07 ± 3.94 (3.04 to 17.97) | 78.3% |
| Placebo | 30 | 8.56 ± 3.79 (2.57 to 16.9) | 76.7% | ||
Subcutaneous every 2 weeks for up to 18 months | |||||
| Definition(s): BW=body weight | |||||
Description of Clinical Studies
The primary efficacy endpoint was “time to treatment failure”. The criteria determining treatment failure were worsening or sustained non-improvement in ocular inflammation, partial improvement with development of sustained ocular co-morbidities or worsening of ocular comorbidities, non-permitted use of concomitant medications, and suspension of treatment for an extended period of time.
Study Results
Clinical Response
Adalimumab injection delayed the time to treatment failure, as compared to placebo (See Figure 8 and Table 54). These results are based on the 2nd interim analysis, which was performed when 90 patients out of a total planned sample size of 114 patients had been randomized in the study.
Table 54 Results of Time to Treatment Failure Analysis in the Pediatric Uveitis Study
Treatment/ Reason for Failure | N | Failure n (%) | Median Time to Failure (Weeks)a | HRb | 99.9% CI for HRb,c | P valuec,d | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Treatment/ Reason for Failure | N | Failure n (%) | Median Time to Failure (Weeks)a | HRb | 99.9% CI for HRb,c | P valuec,d | |||||||
| Placebo | 30 | 18 (60.0) | 24.1 | - | - | - | |||||||
| Anterior segment inflammation or ocular comorbidity | 7 (23.3) | ||||||||||||
| Use of prohibited concomitant medication | 10 (33.3) | ||||||||||||
| Suspension of study treatment | 1 (3.3) | ||||||||||||
| Adalimumab injection e | 60 | 16 (26.7) | NEf | 0.25 | 0.08, 0.79 | <0.0001 | |||||||
| Anterior segment inflammation or ocular comorbidity | 2 (3.3) | ||||||||||||
| Use of prohibited concomitant medication | 11 (18.3) | ||||||||||||
| Suspension of study treatment | 4 (6.7) | ||||||||||||
Definition(s): CI=Confidence Interval; HR=Hazard Ratio a Estimated based on Kaplan-Meier curve. b HR of adalimumab injection versus placebo from proportional hazards regression with treatment as factor. c Significance level of 0.001 was used at the interim analysis based on the Peto-Haybittle stopping rule. d Derived from log rank test. e One adalimumab injection patient had two reasons for treatment failure (use of prohibited concomitant medication and suspension of study treatment). f NE=not estimable. Fewer than half of at-risk subjects had an event. | |||||||||||||
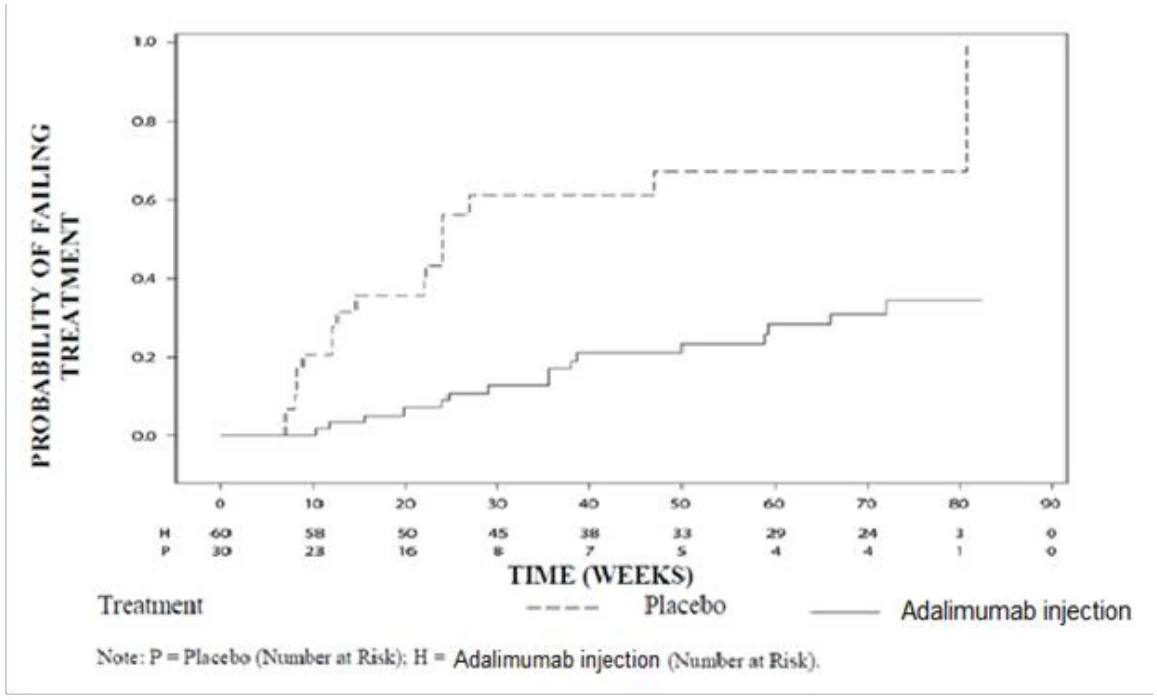
Figure 8 Kaplan-Meier Curves Summarizing Time to Treatment Failure in the Pediatric Uveitis Study
15 MICROBIOLOGY
Not applicable.
16 NON-CLINICAL TOXICOLOGY – REFERENCE BIOLOGIC DRUG
General Toxicology
Acute Toxicity – Single-Dose Studies
Three single-dose toxicity studies (two in mouse and one in rat) were conducted to obtain the qualitative and quantitative information about the acute toxicity profile of adalimumab after single intravenous administration.
In a mouse study, a single dosage of adalimumab (898 mg/kg) or vehicle control (phosphate buffered saline, PBS) was administered via a tail vein (5/sex/group). The animals were examined for clinical signs for 14 days after treatment. Necropsy was performed 14 days after treatment.
At the highest technically feasible dosage of 898 mg/kg adalimumab based on a 10 mL/kg injection volume and the highest available drug concentration, no deaths occurred. No clinical sign was observed that could be attributed to adalimumab. Body weight gains of the drug-treated mice were comparable to those of the control mice. Pathomorphology did not reveal any toxicologically relevant change. The minimal lethal dosage of adalimumab in mice is greater than 898 mg/kg.
A second single-dose study was done in mice and included an investigation of the formation of MAHAs. Four groups of mice (5/sex/group) were included in this study. The animals were treated intravenously with either a single dosage of vehicle (PBS), or 1.6 mg/kg, 16 mg/kg, or 786 mg/kg of adalimumab (drug substance batch AFP603). Clinical signs, especially the hair coat, were assessed. Blood samples were collected before treatment and at Weeks 3, 5, 7, 9, 11, and 13 after drug administration to determine the adalimumab concentration in serum with an ELISA and to detect MAHA formation with two different ELISA techniques. All animals were sacrificed and subjected to gross examination upon termination of the study. Spleen and skin were evaluated histopathologically.
The general deportment of the mice and the body weight gains were not affected by treatment with adalimumab. One male at 1.6 mg/kg died on Day 13 during blood sampling under halothane anesthesia. The death of this animal was considered to be associated with the halothane anesthesia and not associated with the adalimumab treatment. Local hair loss in the nasolabial area associated with loss of tactile hairs was observed in all females at 1.6 mg/kg and four out of five females in the control group from Week 5 onwards. The results indicate that the hair loss is not associated with adalimumab treatment since the same effect also was observed in the control mice.
The serum concentration curve of adalimumab was plotted for one mouse from each group. In the control and 1.6 mg/kg groups, the adalimumab serum concentration was always less than 0.6 mcg/mL, whereas at 16 mg/kg group, 70 mcg/mL was found at Week 3. No adalimumab was detected from Week 5 onwards at this dose. At 786 mg/kg group, a concentration as high as 484 mcg/mL was found at Week 3 and a measurable concentration of adalimumab was found up to nine weeks post injection.
The time course of MAHA development also was measured in one mouse from each group. MAHAs were not detected in the control mouse or any pre-treatment sample. Using a double sandwich (double antigen) MAHA assay (called MAHA-1 assay in the report) sensitive to inhibition by adalimumab in the blood, MAHAs were detected as early as Week 5 for the mouse treated at 1.6 mg/kg and not detected until Week 11 for the mouse treated at 16 mg/kg, whereas MAHAs were not detected at any time point for the mouse treated at 786 mg/kg, which was attributed to the assay interference by the high concentrations of circulating adalimumab. Using a direct capture (sandwich) MAHA assay (called MAHA-2 assay in the report) that is less sensitive to adalimumab interference, MAHAs were detected from Week 5 onwards in mice at 1.6 mg/kg and 16 mg/kg and at Weeks 9 and 13 in the 786 mg/kg mouse. Once the kinetics and titers were determined from the sample mouse of each group, MAHAs in all mice treated with adalimumab were analyzed at a dilution of 1:1000 at Week 5 for the 1.6 mg/kg and 16 mg/kg mice, and at Week 13 for the 786 mg/kg mice by the direct capture MAHA assay. MAHAs were detected in all samples, indicating that all the adalimumab-treated mice were MAHA positive after a single intravenous injection.
In the rat single-dose study, a single dosage of adalimumab (898 mg/kg, drug substance batch AF601-Ex pool) or vehicle control (PBS) was administered via a tail vein (5/sex/group). The animals were examined for clinical signs for 14 days after drug administration. Necropsy was performed 14 days after treatment.
At the highest technically feasible dosage of 898 mg/kg adalimumab based on a 10 mL/kg injection volume and the highest available drug concentration, no deaths occurred. Drug-related clinical signs were not observed. Body weight gains of the drug-treated rats were comparable to those of the control rats. Necropsy showed slightly to moderately enlarged spleens in three males at 898 mg/kg, and slightly enlarged spleens in three males in the control group. Histopathology of the enlarged spleens revealed moderate to marked extramedullary hematopoiesis. These changes were not attributed to the drug treatment because they were observed in the control group as well as in the treatment group.
In summary, adalimumab is well tolerated at the highest technically feasible dose and the minimal lethal dose after a single intravenous injection is greater than 898 mg/kg in mice and rats. Adalimumab is immunogenic in mice after a single intravenous dose.
Long-Term Toxicity – Multiple-Dose Studies
Mouse (Four-Week Study)
In a four-week mouse study, the mice were randomly distributed into three study groups. The highest dose in this study provided 16 times the maximum dosage of 10 mg/kg used in early clinical studies.
The mice were intravenously administered either vehicle control (PBS) or adalimumab (drug substance batch AFP603) once per week on days 1, 8, 15, 22, and 29. The main study group was terminated on Day 30 and the recovery study group was allowed to recover for four weeks without further treatment after the last dose. The mice were observed for drug-related clinical signs at least once daily. Body weight and food consumption was recorded once weekly. Blood samples (0.3 mL) in the main and recovery study groups were collected from the retro-orbital venous plexus under light ether anesthesia on Days 30 and 57 (recovery group only) from mice chosen for hematology, clinical biochemistry and immunogenicity analyses.
There was no clinical sign of toxicity or behavioral changes related to drug treatment. Body weight and body weight gain of drug-treated animals remained in the same range as controls over the treatment and recovery periods.
The results of the toxicokinetic evaluation, using adalimumab level values from pooled serum, revealed that weekly iv administrations of 32, 70.9 and 157.2 mg/kg of adalimumab to mice for four weeks resulted in an increase of serum Cmax and AUC values (Cmax: 1193, 1528, 4231 mcg/mL in males, 794, 2069, 5028 mcg/mL in females; AUC: 66782, 104612, 190342 mcg•h/mL in males, 81598, 120693, 240366 mcg•h/mL in females). A slightly lower terminal half-life was observed for male mice than for female mice (97 to 112 hours versus 134 to 259 hours). The AUC values increased in a slightly less than proportional manner and were somewhat higher in female mice. There was, however, a high degree of variability in the data.
Significant formation of MAHAs was detected in male and female mice in all drug-treated groups starting on the 8th day after the first administration. The level of MAHAs increased with subsequent doses. Significant differences were observed between 32.0 mg/kg and 70.9 mg/kg dosages (p <0.01) and the 32.0 mg/kg and 157.2 mg/kg dosages (p <0.01), but not between the 70.9 mg/kg and 157.2 mg/kg dosages (p >0.05). This indicates that the MAHAs are detected at all dose levels. Whether the differences between dose levels are due to assay interference or true differences in immunogenicity cannot be determined.
Monkey (Four-Week Study)
A four-week study was performed to investigate the potential toxicity of adalimumab in cynomolgus monkeys. A total of 32 monkeys (16 males and 16 females) were distributed randomly into four dosage groups and were administered either the vehicle control (PBS), or adalimumab at 32, 70.9, or 157.2 mg/kg (drug substance batch AFP603) via intravenous injection (vena saphena magna of the right or left hind leg). The injections were given once per week on days 1, 8, 15, 22, and 29 for a total of five doses.
The toxicokinetic results showed a dose-proportional increase of serum maximum concentration (Cmax) of adalimumab and serum AUC. The central volume of distribution (Vc=dose/C(0)) was 39.7 ± 7.9 mL/kg (mean ± standard deviation). The AUCs corresponding to single-dose amounts of 32, 70.9, and 157.2 mg/kg, were 201317 ± 88835, 359667 ± 127283 and 808900 ± 200581 mcg•h/mL, respectively. The terminal half-life was 13.5 ± 4.6 days and the clearance was 0.20 ± 0.07 mL/h/kg. No sex dependency of pharmacokinetic parameters and no influence of dose on total clearance were noted.
Immunohistochemistry data showed a minimal decrease of CD21+B-cells in the spleen follicles of the male monkeys treated with 70.9 and 157.2 mg/kg.) A reduced cytoplasmic immunostaining of IgG and IgM was also observed in the germinal centers of the follicles in most treated monkeys at all doses. No such change was observed in the follicles in the lymph nodes. All these changes were very subtle and generally reversible. Therefore, these changes were considered to be the result of pharmacologically functional effects of adalimumab rather than toxicological effects. No deposits of immune-complexes were found in kidney, lung, liver, skin, spleen, thymus, lymph nodes, skeletal muscle, and heart.
Monkey (39-Week Study)
A 39-week study in cynomolgus monkeys was done to evaluate the potential toxicity and reversibility of any toxic effect of adalimumab. A total of 32 animals (16 males and 16 females) were randomly distributed into four groups and were administered either vehicle control (PBS buffer) or adalimumab at 32, 82.9, or 214.8 mg/kg. The test article or control agent was administered by intravenous injection into a vena saphena magna, once per week for 39 weeks (total of 40 injections).
There were no significant differences in clinical signs of toxicity or behavior and food consumption over the treatment and recovery periods in the drug-treated groups as compared to the control animals. Body weights of the animals treated with 32 and 82.9 mg/kg were not affected as compared with the control animals. In the 214.8 mg/kg group, a slight, transient decrease in the body weight was observed in test Week 4, and completely recovered from test Week 6 onwards. The body weights of the female animals in this group were decreased slightly from test Week 2 onwards. The decreases were not statistically significant at p ≤0.01 as compared with the control animals and were within the normal fluctuation of body weight.
The examination of immune complexes showed a reduced antigen expression of IgG and IgM in the follicular dendritic cells of the spleen in all drug-treated monkeys. Concomitantly, the follicular dendritic cells were reduced in number and the normally dense network was altered. In parallel, the IgG or IgM positive plasma cell count increased slightly in the spleen independently of the different compartments. These changes were considered to be the pharmacologically functional effects of adalimumab rather than toxicological effects.
Toxicokinetic results reported in Report No. MPF/EBB 9741 showed an increase of steady-state serum concentrations and AUC values. At dosages of 32, 82.9, and 214.8 mg/kg of adalimumab, the corresponding Cmax (mean ± standard deviation) at five minutes after the last administration were 2731 ± 467, 6527 ± 2450, 13563 ± 1740 mcg/mL and the corresponding serum AUCs were 304774 ± 74634, 617368 ± 233959, and 1299965 ± 228114 mcg•h/mL, respectively. The corresponding clearances were 0.11 ± 0.04, 0.16 ± 0.07, and 0.17 ± 0.03 mL/h/kg, respectively. The terminal half-life, evaluated from data obtained during the recovery phase of two male and two female monkeys, was 16.2 ± 3.4 days. No sex dependency of pharmacokinetic parameters and no influence of dose on the clearance were noted.
The distribution of adalimumab in the vascular compartment was broad in the lungs, liver, and skin at 214.8 mg/kg. Cartilage staining in the bronchi with anti-adalimumab antibodies was observed in several treated monkeys at 32 mg/kg onwards. In the synovial membrane, adalimumab was detected in the vascular compartment mainly at 214.8 mg/kg, and additionally in one male monkey at 82.9 mg/kg.
Most of the immunohistochemical changes observed in kidneys, spleen, and lungs were found to be reversible. However, the cellular diminution in the thymus in males was partially reversed and did not reach the cellularity of the control animals after a 20-week recovery period. No adalimumab could be detected after the 20-week recovery period in the vessels of the organs and tissues examined.
Carcinogenicity
No carcinogenicity study was performed for adalimumab.
Genotoxicity
In vitro Genotoxicity
The mutagenic potential of adalimumab was tested in the Ames test and in the Escherichia coli reverse mutation assay. These tests are based on the ability of the test article to induce reverse mutations in selected loci of bacteria. Salmonella typhimurium strains TA 98, TA 100, TA 1535, and TA 1537, as well as Escherichia coli strain WP2 uvrA were used. Adalimumab (drug substance batch AF601-Ex pool) was tested at concentrations of 0, 20, 100, 500, 2500 and 5000 mcg/plate. Three plates were used per dose. Positive controls and a vehicle control (PBS buffer) were included in each experiment. Both the standard plate test (Ames test) and preincubation test with and without the addition of an exogenous metabolic activation system (S-9 fraction prepared from the livers of Aroclor 1254 treated rats) were performed. The results were considered positive if the revertant rate of a treatment group was at least twice that of the spontaneous revertant rate (vehicle control), a dose-response relationship occurred, and the experiments were reproducible.
No bacteriotoxic effect, such as reduced His-or Trp-background growth and decreased number of His+ or Trp+ revertants, were observed in adalimumab-treated plates when compared to the vehicle control. There was no increase in the number of mutant colonies under any experimental conditions in any strain of bacteria for the test article, whereas the positive controls showed the expected response when compared to the vehicle control. Therefore, the test substance is not mutagenic either in the Ames test or in the E. coli reverse mutation assays.
In vivo Genotoxicity
The potential clastogenic and spindle poison effects of adalimumab were tested in an in vivo micronucleus assay in NMRI mice after a single intravenous dose. The mice were randomly allocated into eight groups: two vehicle control groups (five mice/sex/group), four treatment groups (five mice/sex/group), and two positive control groups (five mice/group). The mice were intravenously treated once either with the vehicle control (PBS buffer); 224.5, 449.0, or 898 mg/kg (two groups) of adalimumab (drug substance batch AF601-Ex pool); or positive controls of 20 mg cyclophosphamide (two male and three female) or 0.15 mg/kg vincristine (three male and two female). All animals were sacrificed 24 hours after treatment except for one vehicle control group and one 898 mg/kg group, which were sacrificed 48 hours after dosing.
Bone marrow slides were prepared and stained with eosin and methylene solution, followed by Giemsa stain. The slides were examined microscopically for the following parameters: number of polychromatic erythrocytes (PCE), number of PCE containing micronuclei (MN), number of normochromatic erythrocytes (NCE), number of NCE containing MN, number of small micronuclei, and number of large micronuclei. The ratio of PCE to NCE was calculated. The results were considered positive if the following criteria were met: a dose-related and significant increase in the number of micronucleated PCE at the 24-hour and/or 48-hour intervals, and the proportion of cells containing MN exceeded both the values of the concurrent negative control range and the negative historical control range.
The number of PCE and NCE containing MN in the adalimumab-treated groups was not significantly different from the concurrent, negative controls at any of the sacrificed intervals. However, the percentage of small MN in PCE in the cyclophosphamide-treated group and the percentage of large MN in PCE in the vincristine-treated group increased significantly as compared with the vehicle control. The ratio of PCE to NCE in all dose groups was always in the same range as that of the control values, suggesting normal erythropoiesis.
The results indicate that adalimumab does not have clastogenic activity or spindle poison effects. Also, no inhibition of erythropoiesis induced by the treatment with adalimumab was observed in NMRI mice.
Reproduction and Teratology
In pregnant monkeys adalimumab was distributed into the serum of the fetus and into the amnion fluid showing a distribution pattern that would be expected of a human IgG in a pregnant woman. No drug-related toxicity was observed. Distribution of adalimumab into the milk was not determined.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Humira®, Product Monograph, Control number: 262924; dated: September 16, 2022, AbbVie Corporation.