


Product Monograph - Imipenem and Cilastatin for Injection, USP (Sterimax)
INDICATIONS AND CLINICAL USE
Imipenem and Cilastatin for Injection, USP may be indicated in the treatment of serious infections when caused by sensitive strains of bacteria. Where considered necessary, therapy may be initiated on the basis of clinical judgment before results of sensitivity testings are available. Continuation of therapy should be reevaluated on the basis of bacteriological findings and of the patient's clinical condition.
Imipenem is active in vitro against a wide range of gram-positive and gram-negative aerobic and anaerobic bacteria, including most strains which are beta-lactamase producing. Patients have responded while under treatment with imipenem and cilastatin sodium for injection for single or mixed infections of the following body systems, when they were associated with a number of pathogenic species and strains of the genera listed:
- 1. Lower Respiratory Tract Infections
- 2. Urinary Tract Infections
- 3. Intra-Abdominal Infections
- 4. Gynecological Infections
- 5. Septicemia
- 6. Endocarditis caused by Staphylococcus aureus
- 7. Bone and Joint Infections
- 8. Skin Structure Infections
Imipenem and Cilastatin for Injection, USP is not indicated for the treatment of meningitis.
Gram-positive Aerobes
Nocardia asteroides
Staphylococcus (excluding many strains which are methicillin resistant)
Streptococcus
[Enterococcus faecium (formerly Streptococcus faecium) is not susceptible to imipenem and cilastatin sodium for injection.
Gram-negative Aerobes
Acinetobacter
Citrobacter
Enterobacter
Escherichia coli
Haemophilus influenzae
Haemophilus parainfluenzae
Klebsiella
Morganella morganii
Proteus (indole positive and indole negative strains)
Providencia
Pseudomonas aeruginosa
Serratia marcescens
Gram-positive Anaerobes
Clostridium (excluding C. difficile)
Peptococcus
Peptostreptococcus
Gram-negative Anaerobes
Bacteroides fragilis
Bacteroides (non fragilis)
To reduce the development of drug-resistant bacteria and maintain the effectiveness of
Imipenem and Cilastatin for Injection, USP and other antibacterial drugs, Imipenem and Cilastatin for Injection, USP should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
CONTRAINDICATIONS
Imipenem and Cilastatin for Injection, USP is contraindicated in patients who have shown hypersensitivity to either component of this product.
WARNINGS
General
SEVERE AND OCCASIONALLY FATAL (ANAPHYLACTIC) REACTIONS HAVE BEEN REPORTED WITH MOST BETA-LACTAM ANTIBIOTICS. THESE REACTIONS ARE MORE APT TO OCCUR IN PERSONS WITH A HISTORY OF SENSITIVITY TO MULTIPLE ALLERGENS.
THERE IS SOME CLINICAL AND LABORATORY EVIDENCE OF PARTIAL CROSS-ALLERGENICITY BETWEEN IMIPENEM AND CILASTATIN SODIUM FOR INJECTION, AND THE OTHER BETA-LACTAM ANTIBIOTICS. BEFORE INITIATING THERAPY WITH IMIPENEM AND CILASTATIN FOR INJECTION, USP CAREFUL INQUIRY SHOULD BE MADE CONCERNING PREVIOUS HYPERSENSITIVITY REACTION TO BETA-LACTAM ANTIBIOTICS, PENICILLINS AND CEPHALOSPORINS AND OTHER ALLERGENS.
IF AN ALLERGIC REACTION TO IMIPENEM AND CILASTATIN FOR INJECTION, USP OCCURS, THE DRUG SHOULD BE DISCONTINUED AND APPROPRIATE MEASURES UNDERTAKEN. SERIOUS ANAPHYLACTIC REACTIONS REQUIRE IMMEDIATE TREATMENT WITH EPINEPHRINE AND OTHER EMERGENCY MEASURES.
Seizure Potential
Seizures and other CNS adverse experiences, such as confusional states and myoclonic activity, have been reported during treatment with imipenem and cilastatin sodium for injection (See PRECAUTIONS and ADVERSE REACTIONS).
Case reports in the literature have shown that co-administration of carbapenems, including imipenem, to patients receiving valproic acid or divalproex sodium results in a reduction in serum valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction. In some cases of co-administration of imipenem with valproic acid, breakthrough seizures have occurred. Increasing the dose of valproic acid or divalproex sodium may not be sufficient to overcome this interaction. The concomitant use of imipenem and valproic acid/divalproex sodium is generally not recommended. Anti-bacterials other than carbapenems should be considered to treat infections in patients whose seizures are well controlled on valproic acid or divalproex sodium. If administration of Imipenem and Cilastatin for Injection, USP is necessary, supplemental anti-convulsant therapy should be considered (see DRUG INTERACTIONS / Drug-Drug Interactions).
Gastrointestinal
Clostridium difficile-associated disease
Clostridium difficile-associated disease (CDAD) has been reported with the use of many antibacterial agents, including imipenem and cilastatin sodium for injection. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases. (see ADVERSE REACTIONS).
Susceptibility/Resistance
Development of Drug Resistant Bacteria
Prescribing Imipenem and Cilastatin for Injection, USP in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
PRECAUTIONS
General
Prolonged use of Imipenem and Cilastatin for Injection, USP may result in overgrowth of resistant organisms. Repeated evaluation of the patient's condition is essential. If superinfection occurs during therapy, appropriate measures should be taken.
CNS adverse experiences such as myoclonic activity, confusional states, or seizures have been reported with imipenem and cilastatin sodium for injection especially when recommended dosages based on renal function and body weight were exceeded. These experiences have occurred most commonly in patients with CNS disorders (e.g., brain lesions or history of seizures) and/or who have compromised renal function. However, there were rare reports in which there was no recognized or documented underlying CNS disorder.
When recommended doses were exceeded, adult patients with creatinine clearances of ≤20 mL/min/1.73 m2, whether or not undergoing hemodialysis, had a higher risk of seizure activity than those without impairment of renal function. Close adherence to recommended dosage schedules is urged especially in patients with known factors that predispose to seizures (see DOSAGE AND ADMINISTRATION).
Patients with creatinine clearances of ≤5 mL/min/1.73 m2 should not receive Imipenem and Cilastatin for Injection, USP unless hemodialysis is instituted within 48 hours.
For patients on hemodialysis, Imipenem and Cilastatin for Injection, USP is recommended only when the benefit outweighs the potential risk of seizures.
Anticonvulsant therapy should be continued in patients with a known seizure disorder. If focal tremors, myoclonus, or seizures occur, patients should be evaluated neurologically and placed on anticonvulsant therapy if not already instituted. If CNS symptoms continue, the dosage of Imipenem and Cilastatin for Injection, USP should be decreased or discontinued (see DRUG INTERACTIONS / Drug-Drug Interactions).
Use in Patients with Impaired Renal Function
Dosage in patients with impaired renal function is based on the severity of infection but the maximum daily dose varies with the degree of renal functional impairment. Adult patients with impaired renal function, as judged by creatinine clearance ≤70 mL/min/1.72m2, require adjustment (see DOSAGE AND ADMINISTRATION / Dosage / Dosage in Patients with Renal Insufficiency).
Special Populations
Pregnant Women: The use of Imipenem and Cilastatin for Injection, USP in pregnant women has not been studied. Imipenem and Cilastatin for Injection, USP should be used during pregnancy only if the potential benefit justifies the potential risk to the mother and fetus.
Reproduction studies with bolus I.V. doses suggest an apparent intolerance to imipenem and cilastatin sodium for injection (including emesis, inappetence, body weight loss, diarrhea and death) at doses equivalent to the average human dose in pregnant rabbits and cynomolgus monkeys that is not seen in non-pregnant animals in these or other species. In other studies, imipenem and cilastatin sodium for Injection was well tolerated in equivalent or higher doses (up to 11 times the average human dose) in pregnant rats and mice (see REPRODUCTION STUDIES under TOXICOLOGY).
Nursing Women:
Imipenem has been detected in human milk. If the use of Imipenem and Cilastatin for Injection, USP is deemed essential, the patient should stop nursing.
Pediatric Patients (≥ 3 months of age):
Efficacy and tolerability in infants under the age of 3 months have not yet been established; therefore, Imipenem and Cilastatin for Injection, USP is not recommended in the pediatric age group below the age of 3 months. Clinical data are insufficient to recommend the use of imipenem and cilastatin sodium for injection for pediatric patients with impaired renal function (serum creatinine >2mg/dL) (see DOSAGE AND ADMINISTRATION / Dosage in Infants and Children).
Geriatric (≥65 years old): No dosage adjustment is required solely on the basis on age (see, DOSAGE and ADMINISTRATION, Geriatric). This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
DRUG INTERACTIONS
Drug-Drug Interactions
Generalized seizures have been reported in patients who received ganciclovir and imipenem and cilastatin sodium for injection. These drugs should not be used concomitantly unless the potential benefits outweigh the risks.
Case reports in the literature have shown that co-administration of carbapenems, including imipenem, to patients receiving valproic acid or divalproex sodium results in a reduction of serum valproic acid concentrations. The valproic acid concentrations may drop below the therapeutic range as a result of this interaction. In some cases of co-administration of Imipenem with valproic acid, breakthrough seizures have occurred. The mechanism of this interaction is unknown (See PRECAUTIONS - General).
Concomitant administration of imipenem and cilastatin sodium for injection and probenecid results in only minimal increases in plasma levels of imipenem and plasma half-life. It is not recommended that probenecid be given with Imipenem and Cilastatin for Injection USP.
Imipenem and Cilastatin for Injection, USP should not be mixed with or physically added to other antibiotics. Imipenem and cilastatin sodium for injection has been administered concomitantly with some antibiotics, such as aminoglycosides.
There is no evidence to suggest that association of Imipenem and Cilastatin for Injection, USP with any other beta-lactam antibiotics has any therapeutic advantage.
ADVERSE REACTIONS
Adults
Imipenem and Cilastatin for Injection, USP are generally well tolerated. The following adverse reactions were reported on 1,723 patients treated in clinical trials. Many of these patients were severely ill and had multiple background diseases and physiological impairments, making it difficult to determine causal relationship of adverse experiences to therapy with imipenem and cilastatin sodium for injection.
Local Adverse Reactions
Adverse local clinical reactions that were reported as possibly, probably or definitely related to therapy with imipenem and cilastatin sodium for injection were:
| Incidence (%) | |
|---|---|
Phlebitis/thrombophlebitis Pain at the injection site Erythema at the injection site Vein induration Infused vein infection | 3.1 0.7 0.4 0.2 0.1 |
Systemic Adverse Reactions
Adverse clinical reactions that were reported as possibly, probably or definitely related to imipenem and cilastatin sodium for injection were:
| Incidence (%) | ||
|---|---|---|
| Gastrointestinal | ||
Nausea Diarrhea Vomiting Tongue papillar hypertrophy Pseudomembranous colitis (see WARNINGS) Hemorrhagic colitis Gastroenteritis Abdominal pain Glossitis Heartburn Pharyngeal pain Increased salivation | 2.0 1.8 1.5 <0.2 0.1 <0.1 <0.1 <0.1 <0.1 <0.1 <0.1 <0.1 | |
| CNS | ||
Fever Dizziness Seizures (see PRECAUTIONS) Somnolence Confusion Myoclonus Vertigo Headache Encephalopathy Paresthesia | 0.5 0.3 0.4 0.2 <0.2 0.1 0.1 0.1 <0.1 <0.1 | |
| Special Senses | ||
| Incidence (%) | ||
|---|---|---|
Transient hearing loss in patients with impaired hearing Tinnitus | <0.1 <0.1 | |
| Respiratory | ||
Dyspnea Hyperventilation Thoracic spine pain | 0.1 <0.1 <0.1 | |
| Cardiovascular | ||
Hypotension Palpitations Tachycardia | 0.4 0.1 <0.1 | |
| Renal | ||
Oliguria/anuria Polyuria | <0.1 <0.1 | |
| Skin | ||
Rash Pruritus Urticaria Skin texture changes Candidiasis Erythema multiforme Facial edema Flushing Cyanosis Hyperhidrosis Pruritus vulvae | 0.9 0.3 0.2 0.1 0.1 <0.1 <0.1 <0.1 <0.1 <0.1 <0.1 | |
| Body as a whole | ||
Polyarthralgia Asthenia/weakness | <0.1 <0.1 | |
The most frequently reported systemic adverse clinical reactions that were reported were nausea, diarrhea, vomiting, rash, fever, hypotension, seizures, dizziness pruritus, urticaria and somnolence.
Adverse Laboratory Changes
Adverse laboratory changes, without regard to drug relationship, that were reported during clinical trials were:
Hepatic: Increased ALT (SGPT), AST (SGOT), alkaline phosphatase, bilirubin and LDH.
Hemic: Increased eosinophils, positive Coombs' test, leukopenia (decreased WBC), neutropenia (decreased neutrophils), increased WBC, increased platelets, thrombocytopenia (decreased platelets), decreased hemoglobin and hematocrit, increased monocytes, abnormal prothrombin time, increased lymphocytes, increased basophils.
Electrolytes: Decreased serum sodium, increased potassium, increased chloride.
Renal: Increased blood urine nitrogen (BUN), serum creatinine.
Urinalysis: Presence of urine protein, urine red blood cells, urine white blood cells, urine casts, urine bilirubin, and urine urobilinogen.
Post-Market Adverse Drug Reactions
The following reactions have been reported since the drug was marketed, but occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, that possibility cannot be excluded. Therefore, these observations are listed to serve as alerting information to physicians and pharmacists:
- Acute renal failure. The role of imipenem and cilastatin sodium for injection in changes in renal function is difficult to assess, since factors predisposing to pre-renal azotemia or to impaired renal function usually have been present.
- Anaphylactic reactions
- Angioneurotic edema
- Agitation
- Agranulocytosis
- Bone marrow depression
- Chest discomfort
- Drug fever
- Dyskinesia
- Exfoliative dermatitis
- Hallucinations
- Hearing loss
- Hemolytic anemia
- Hepatic failure
- Hepatitis (including Fulminant hepatitis)
- Jaundice
- Pancytopenia
- Psychic disturbances
- Staining of teeth and/or tongue
- Stevens-Johnson syndrome
- Taste perversion
- Toxic epidermal necrolysis
- Tremor
- Urine discoloration
Pediatrics (≥3 months of age):
In studies of 178 pediatric patients, the most common clinical adverse experiences (>1%) without regard to Drug relationship were as follows:
Digestive System: diarrhea (3.9%), gastroenteritis (1.1%), vomiting (1.1%)
Skin: rash (2.2%), irritation at IV site (1.1%)
Urogenital System: urine discoloration (1.1%)
Cardiovascular System: phlebitis (2.2%)
In this age group abnormal laboratory values for hemoglobin, hematocrit, neutrophils, eosinophils, platelet count, urine protein, serum creatinine, BUN, AST and ALT occurred during therapy*.
*pre-therapy values were normal
OVERDOSAGE
In case of overdosage, discontinue Imipenem and Cilastatin for Injection, USP, treat symptomatically and institute supportive measures as required. Imipenem-cilastatin sodium is cleared by hemodialysis. Usefulness of this procedure in the overdosage setting is questionable.
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
|---|
DOSAGE AND ADMINISTRATION
Dosage
General
The dosage recommendations for Imipenem and Cilastatin for Injection, USP represent the quantity of imipenem to be administered by I.V. infusion only. An equivalent amount of cilastatin is also present in the solution.
The dosage of Imipenem and Cilastatin for Injection, USP should be determined by the severity of the infection, renal function, body weight, the antibiotic susceptibility of the causative organism(s) and the condition of the patient. Doses cited are based on body weight of 70 kilos.
The median duration of treatment with imipenem and cilastatin sodium for injection in clinical trials for infections of the various body systems ranged from 6 to 10 days except for endocarditis and bone and joint infections for which the median duration of treatment was 4 weeks.
Adults with Normal Renal Function and Body Weight of ≥70 kg.
The recommended daily dose is 1 to 2 g administered in equally divided doses every 6 to 8 hours for fully susceptible organisms (see Table 1).
TABLE 1 ADULT DOSAGE OF IMIPENEM AND CILASTATIN FOR INJECTION, USP
| I.V. Administration | |||
|---|---|---|---|
| Severity of infection | Dose (mg of Imipenem) | Dosage Interval | Daily Dose |
| Mild | 250 mg | 6 h | 1.0 g |
| I.V. Administration | |||
|---|---|---|---|
| Severity of infection | Dose (mg of Imipenem) | Dosage Interval | Daily Dose |
| Moderate | 500 mg | 8 h | 1.5 g |
| Severe (fully susceptible) | 500 mg | 6 h | 2.0 g |
| Severe* infections due to less susceptible organisms or life threatening conditions | 1000 mg 1000 mg | 8 h 6 h | 3.0 g 4.0 g |
* Primarily some strains of P. aeruginosa.
The maximum daily dose should not exceed 4 g or 50 mg/kg, whichever is less.
Geriatric Patients
The recommended dosage of Imipenem and Cilastatin for Injection, USP in elderly patients with normal renal function is the same as given for adults above. Renal status of elderly patients may not be accurately portrayed by measurement of BUN or creatinine alone. Determination of creatinine clearance is suggested to provide guidance for dosing in such patients (see PRECAUTIONS / Geriatrics).
Adults with Impaired Renal Function and/or Body Weight < 70 kg
Patients with creatinine clearances of ≤ 5 mL/min/1.73 m2 (≤ 0.08 mL/s/1.73 m2) should not receive Imipenem and Cilastatin for Injection, USP unless hemodialysis is instituted within 48 hours. Both imipenem and cilastatin are cleared from the circulation during hemodialysis. The patient should receive Imipenem and Cilastatin for Injection, USP after hemodialysis and at 12 hour intervals timed from the end of that hemodialysis session. Dialysis patients, especially those with background CNS disease, should be carefully monitored; for patients on hemodialysis, Imipenem and Cilastatin for Injection, USP is recommended only when the benefit outweighs the potential risk of seizures (see PRECAUTIONS). Currently, there are inadequate data to recommend the use of Imipenem and Cilastatin for Injection, USP in patients undergoing peritoneal dialysis.
TABLE 2: MAXIMUM DOSAGE OF IMIPENEM AND CILASTATIN FOR INJECTION, USP IN RELATION TO RENAL FUNCTION
| RENAL FUNCTION | CREATININE CLEARANCE mL/min/1.73 m2 (mL/s/1.73 m2 ) | MAXIMUM TOTAL DAILY DOSAGE for infections due to fully susceptible organisms | MAXIMUM TOTAL DAILY DOSAGE for infections due to less susceptible organisms** |
|---|---|---|---|
| Mild impairment | 31 - 70 (0.52 - 1.17) | 1.5 g (0.5 g q8h) | 2.0 g (0.5 g q6h) |
| Moderate impairment | 21 – 30 (0.35 - 0.50) | 1.0 g (0.5 g q12h) | 1.5 g (0.5 g q8h) |
| Severe impairment* | 0 – 20 (0 - 0.33) | 0.5 g (0.25 g q12h) | 1.0 g (0.5 g q12h) |
* Patients with creatinine clearance of 6 to 20 mL/min/1.73 m 2 (0.1 - 0.3 mL/s/1.73 m2) should be treated with 250 mg (or 3.5 mg/kg whichever is lower) every 12 hours for most pathogens. When the 500 mg dose is used in these patients, there may be an increased risk of seizures.
** Primarily some strains of P. aeruginosa.
A further proportionate reduction in dose administered must be made for patients with a body weight <70kg. The reduction for body weight is especially important for patients with much lower body weight and/or moderate/severe renal insufficiency.
When only the serum creatinine level is available, the following formula (based on sex, weight, and age of the patient) may be used to convert this value into creatinine clearance (mL/min). The serum creatinine should represent a steady state of renal function.
Males: Weight (kg) x (140 - age)
72 x serum creatinine (mg/100 mL)
Females: 0.85 x above value.
When using the International System of units (SI), the estimated creatinine clearance (mL/s) in males can be calculated as follows:
(lean body weight, kg) x (140 - age, years) x 1.4736
(72) x (serum creatinine concentration, µmol/L)
and in females, the estimated creatinine clearance (mL/s) is:
(lean body weight, kg) x (140 - age, years) x 1.2526
(72) x (serum creatinine concentration, µmol/L)
Imipenem and cilastatin sodium for injection are cleared by hemodialysis. After each dialysis session the dosage schedule should be restarted.
Pediatric Patients (≥ 3 months of age) The recommended total daily dosage of Imipenem and Cilastatin for Injection, USP in children and infants 3 months of age and older is 60 to 100 mg/kg of body weight divided into 4 equal doses given at six hour intervals. The higher dosages should be used for infants and young children. The total daily dosage should not exceed 2 grams. Clinical data are insufficient to recommend an optimum dose for infants and children with impaired renal function.
Imipenem and Cilastatin for Injection, USP is not recommended for the therapy of meningitis. If meningitis is suspected, an appropriate antibiotic should be used.
Imipenem and Cilastatin for Injection, USP may be used in children with sepsis as long as they are not suspected of having meningitis.
Administration
CAUTION: CONTENTS OF VIALS NOT FOR DIRECT INFUSION.
Each reconstituted 250 mg or 500 mg dose should be given by intravenous infusion over 20 to 30 minutes. Each 1000 mg dose should be infused over 40 to 60 minutes. In patients who develop nausea during the infusion, the rate of infusion may be slowed (for reconstitution, see PHARMACEUTICAL INFORMATION / CHEMISTRY / Reconstitution).
PHARMACEUTICAL INFORMATION
CHEMISTRY
Proper name: Imipenem and Cilastatin for Injection, USP
Chemical names:
Imipenem
[5R-[5α,6α(R*)]]-6-(1-Hydroxyethyl)-3-[[2-[(iminomethyl)amino]ethyl]thio]-7-oxo-1-azabicyclo[3.2.0]hept-2-ene-2-carboxylic acid monohydrate;
1-Azabicyclo[3.2.0]hept-2-ene-2-carboxylic acid,6-(1-hydroxyethyl)-3-[[2-(iminomethyl) amino]ethyl]thio]-7-oxo-,monohydrate;
Cilastatin sodium
[R-[R*,S*-(Z)]]-Sodium (Z)-7-[[(R)-2-amino-2-carboxyethyl]thio]-2-[(S)-2,2-
dimethylcyclopropanecarboxamido]-2-heptenoate;
2-Heptenoic acid,7-[(2-amino-2-carboxyethyl)thio]-2-[[(2,2-dimethylcyclopropyl) carbonyl]amino]-,monosodium salt;
Structural formula:
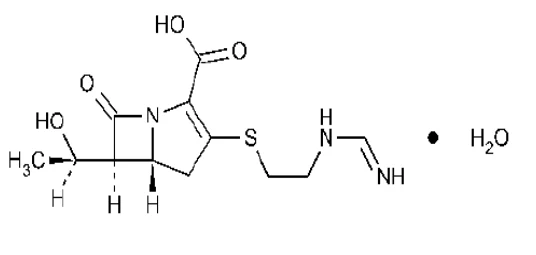
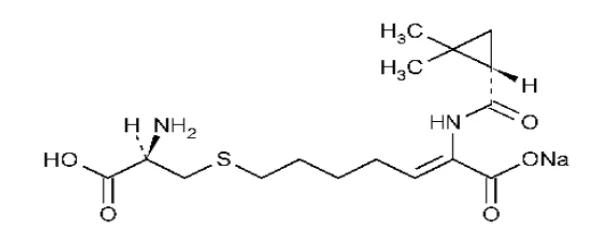
Molecular Formulae:
C12 H17N3O4S.H2O C16H25N2O5SNa
Molecular Weights:
317.36 g/mol 380.44 g/mol
Descriptions:
| Imipenem is a white to almost white or pale yellow powder. Sparingly soluble in water and slightly soluble in methanol. | Cilastatin is a white or light yellow hygroscopic, amorphous powder. It is very soluble in water and in methanol, practically insoluble in acetone and methylene chloride. |
|---|
Composition: Imipenem and Cilastatin sodium are present in Imipenem and Cilastatin for Injection, USP in a 1:1 ratio by weight with sodium bicarbonate as a buffer.
Imipenem and Cilastatin for Injection, USP – 250 mg/vial: Each vial contains sterile buffered Mixture of Imipenem and Cilastatin Sodium equivalent to Imipenem 250 mg and Cilastatin 250 mg.
Imipenem and Cilastatin for Injection, USP – 500 mg/vial: Each vial contains sterile buffered Mixture of Imipenem and Cilastatin Sodium equivalent to Imipenem 500 mg and Cilastatin 500 mg.
Reconstitution: Imipenem and Cilastatin for Injection, USP is supplied in vials of either 250 mg or 500 mg Imipenem equivalent and Cilastatin equivalent when reconstituted.
Vials - Imipenem and Cilastatin for Injection, USP
Contents of the vials must be suspended and transferred to 100 mL of an appropriate infusion solution.
A suggested procedure is to transfer approximately 10 mL from the 100 mL of the appropriate infusion solution to the vial (see list of diluents under COMPATIBILITY AND STABILITY). Shake well. Return the resulting 10 mL of suspension to the remaining 90 mL of the infusion solution.
Repeat, using 10 mL of the diluted suspension, to ensure complete transfer of the contents of the vial to the infusion solution.
CAUTION: CONTENTS OF VIALS NOT FOR DIRECT INFUSION.
COMPATIBILITY AND STABILITY
List of diluents
- 0.9% Sodium Chloride Injection
- 5% or 10% Dextrose Injection
- 5% Dextrose Injection with 0.02% sodium bicarbonate solution
- 5% Dextrose with 0.9% Sodium Chloride Injection
- 5% Dextrose with 0.225% or 0.45% saline solution
- 5% Dextrose with 0.15% potassium chloride solution
- Mannitol 5% and 10%
Reconstituted solutions
Solutions of Imipenem and Cilastatin for Injection, USP range from colourless to yellow. Variations of colour within this range do not affect the potency of the product.
Imipenem and Cilastatin for Injection, USP, as supplied in vials and reconstituted as above maintain satisfactory potency for four hours at room temperature and for 24 hours under refrigeration (4oC).
AVAILABILITY OF DOSAGE FORMS
Imipenem and Cilastatin for Injection, USP is supplied as a sterile powder mixture in vials containing Imipenem anhydrous and Cilastatin sodium with sodium bicarbonate as a buffer as follows:
250 mg Imipenem equivalent and 250 mg Cilastatin equivalent in vials.
500 mg Imipenem equivalent and 500 mg Cilastatin equivalent in vials.
STORAGE
The dry powder should be stored at 15°C - 30°C. Protect from light.
MICROBIOLOGY
Mechanism of action
Imipenem and Cilastatin for Injection, USP consists of two components: Imipenem and Cilastatin sodium in a 1:1 ratio by weight.
Imipenem is a B-lactam carbapenem antibacterial which is also referred to as N- formimidoyl-thienamycin. It is a semi-synthetic derivative of thienamycin, the parent compound produced by the filamentous bacterium Streptomyces cattleya.
Imipenem exerts its bactericidal activity by inhibiting bacterial cell wall synthesis in Gram-positive and Gram-negative bacteria through binding to penicillin-binding proteins (PBPs).
Cilastatin sodium is a competitive, reversible and specific inhibitor of dehydropeptidase-I, the renal enzyme which metabolizes and inactivates imipenem. It is devoid of intrinsic antibacterial activity.
Mechanism of resistance
Bacterial resistance to imipenem which has been observed clinically may be due to the following:
- Decreased permeability of the outer membrane of Gram-negative bacteria (due to diminished production of porins)
- Imipenem may be actively removed from the cell with an efflux pump.
- Reduced affinity of PBPs to imipenem
- Imipenem is stable to hydrolysis by most beta-lactamases, including penicillinases and cephalosporinases produced by gram-positive and gram-negative bacteria, with the exception of some carbapenem hydrolysing beta-lactamases known as carbapenemases. Species resistant to other carbapenems do generally express co-resistance to imipenem. There is no target-based cross-resistance between imipenem and agents of the quinolone, aminoglycoside, macrolide and tetracycline classes.
Interaction with Other Antimicrobials
Antagonism by imipenem of the activity of other beta-lactam antibiotics has been observed, in vitro, when tested against species of Enterobacteriaceae and Pseudomonas aeruginosa that contain Type-I chromosomal encoded cephalosporinase. The antagonism results from the reversible induction of the cephalosporinase by subinhibitory levels of imipenem. The organisms with induced levels of cephalosporinase, however, remain susceptible to imipenem.
Synergistic interaction with other antibiotics such as amino-glycosides has been observed in gram-negative species including P. aeruginosa and gram-positive species such as E. faecalis and Nocardia asteroides.
Spectrum of activity
Imipenem has in vitro activity against a wide range of gram-positive and gram-negative organisms. Imipenem has been shown to be active against most strains of the following microorganisms both in vitro and in clinical infections as described in the INDICATIONS AND CLINICAL USE section.
Gram-positive aerobes:
- Nocardia asteroides
- Staphylococcus (excluding methicillin resistant strains)
- Streptococcus
[Enterococcus faecium (formerly Streptococcus faecium) is not susceptible to Imipenem and Cilastatin for Injection, USP.
Gram-negative aerobes:
- Acinetobacter spp.
- Citrobacter spp.
- Enterobacter spp.
- Escherichia coli
- Haemophilus influenzae
- Haemophilus parainfluenzae
- Klebsiella spp.
- Morganella morganii
- Proteus vulgaris
- Providencia spp.
- Pseudomonas aeruginosa
- Serratia marcescens
Gram-positive anaerobes:
- Clostridium spp. (excluding C. difficile)
- Peptococcus spp.
- Peptostreptococcus spp.
Gram-negative anaerobes:
- Bacteroides spp., including B. fragilis
The following in vitro data are available, but their clinical significance is unknown: Imipenem exhibits in vitro minimum inhibitory concentrations (MICs) of 4 μg/mL or less against most (≥90%) strains of the following microorganisms; however, the safety and effectiveness of imipenem in treating clinical infections due to these microorganisms have not been established in adequate and well-controlled clinical trials.
Gram-positive aerobes:
- Bacillus spp.
- Listeria monocytogenes
- Staphylococcus saprophyticus
- Group C streptococci
- Group G streptococci
- Viridans group streptococci
Gram-negative aerobes:
- Aeromonas hydrophila
- Alcaligenes spp.
- Capnocytophaga spp.
- Gardnerella vaginalis
- Haemophilus ducreyi
- Neisseria gonorrhoeae including penicillinase-producing strains
- Pasteurella spp.
- Providencia stuartii
Gram-positive anaerobes:
- Bifidobacterium spp.
- Eubacterium spp.
- Propionibacterium spp.
Gram-negative anaerobes:
- Fusobacterium spp.
- Prevotella bivia
- Prevotella disiens
- Prevotella melaninogenica
- Veillonella spp.
Stenotrophomonas maltophilia (formerly Xanthomonas maltophilia, formerly Pseudomonas maltophilia), Burkholderia cepacia (formerly Pseudomonas cepacia), Methicillin-resistant S. aureus and S. epidermidis, Enterococcus faecium (formerly Streptococcus faecium), Flavobacterium spp., Corynebacterium (J.K.), Fusobacterium varium, and species of Mycobacterium and Chlamydia are species generally reported insensitive to imipenem.
Susceptibility Testing
Bacterial susceptibility to imipenem is conducted via standardized methods. Dilution and diffusion techniques are used for aerobes and dilution techniques only for anaerobes.
Dilution Techniques
Quantitative methods are used to determine antimicrobial minimum inhibitory concentrations (MICs). These MICs provide estimates of the susceptibility of bacteria to antimicrobial compounds. The MICs should be determined using a standardized procedure. Standardized procedures are based on a dilution method (broth or agar) or equivalent with standardized inoculum concentrations and standardized concentrations of imipenem powder. The MIC values should be interpreted according to criteria and methods provided in Table 3
Diffusion Techniques
Quantitative methods that require measurement of zone diameters also provide reproducible estimates of the susceptibility of bacteria to antimicrobial compounds. One such standardized procedure requires the use of standardized inoculum concentrations. This procedure uses paper disks impregnated with 10 mcg imipenem to test the susceptibility of microorganisms to imipenem. The disk diffusion interpretive criteria and methods are provided in Table 3.
TABLE 3: CLSI INTERPRETIVE BACTERIALSUSCEPTIBILITY CRITERIA FOR IMIPENEMa
| Pathogen a | Dilution Test (Minimum Inhibitory Concentrations MICs in mcg/mL) | Disk Diffusion Test (zone diameters in mm) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| S | I | R | S | I | R | ||||||||||||
| Enterobacteriaceae | ≤ 1.0 | 2.0 | ≥ 4.0 | ≥ 23 | 20-22 | ≤ 19 | |||||||||||
| Pseudomonas aeruginosa | ≤ 2 | 4 | ≥ 8 | ≥ 19 | 16-18 | ≤ 15 | |||||||||||
| Acinetobacter spp. | ≤ 2 | 4 | ≥ 8 | ≥ 22 | 19-21 | ≤ 18 | |||||||||||
| Haemophilus influenza and H. parainfluenzae c | ≤ 4 | - | - | ≥ 16 | - | - | |||||||||||
| Streptococcus pneumoniaeb | ≤ 0.12 | 0.25- 0.5 | ≥ 1 | - | - | - | |||||||||||
| Anaerobes | ≤ 4 | 8.0 | ≥ 16.0 | - | - | - | |||||||||||
a reference is made to those pathogens listed in INDICATIONS section of product monograph; broth and agar dilution methods apply to aerobes other than Haemophilus spp. and Streptococcus pneumoniae for which only broth dilution applies; the numbers presented for anaerobes reference agar dilution; a hyphen indicates Not Applicable; for further details and applicable laboratory methods see CLSI (Clinical and Laboratory Standards Institute) documents: M7-A7: Methods for dilution antimicrobial susceptibility tests for bacteria that grow aerobically (Jan 2006); M11- A7: Methods for antimicrobial susceptibility testing for anaerobic bacteria (Jan 2007); M100-S24: Performance standards for antimicrobial susceptibility testing (Jan 2014)
b there are no CLSI interpretive criteria for MIC testing of beta hemolytic Streptococcus spp. or viridans group Streptococci against imipenem (ref CLSI ref M100-S24, table 2 H1 and table 2 H2);
c absence of data on resistant strains precludes defining any other category than ‘susceptible’ (see CLSI document M100-S24, table 2E)
A report of “Susceptible’’ indicates that the pathogen is likely to be inhibited if the antimicrobial compound in blood reaches the concentrations usually achievable. A report of “Intermediate” indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible drugs, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high dosage of drug can be used. This category also provides a buffer zone which prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of ‘Resistant’ indicates that the pathogen is not likely to be inhibited if the antimicrobial compound in the blood reaches the concentrations usually achievable; other therapy should be selected.
Quality Control
Standardized susceptibility test procedures require the use of quality control microorganisms to control the technical aspects of the test procedures. Standard imipenem powder as used in the dilution test and 10 mcg imipenem impregnated discs as used in the diffusion test should provide the following range of values noted in Table 4
TABLE 4: ACCEPTABLE QUALITY CONTROL ORGANISMS AND TEST RANGES FOR IMIPENEM
| QC Strain | ATCC® a | Dilution Test (MICs in mcg/mL) | Disk Diffusion Test (zone diameters in mm) |
|---|---|---|---|
| Enterococcus faecalis b | 29212 | 0.5-2 | Not Applicable |
| Staphylococcus aureus b | 29213 | 0.015-0.06 | Not Applicable |
| Streptococcus pneumoniae c | 49619 | 0.03-0.12 | Not Applicable |
| Escherichia coli b | 25922 | 0.06-0.25 | 26-32 |
| Haemophilus influenzae c | 49766 | 0.25-1 | Not Applicable |
| Haemophilus influenzae c | 49247 | Not Applicable | 21-29 |
| Pseudomonas aeruginosa b | 27853 | 1-4 | 20-28 |
| Bacteroides fragilis d | 25285 | 0.03-0.125 | Not Applicable |
| Bacteroides thetaiotaomicron d | 29741 | 0.125-0.5 | Not Applicable |
| Eubacterium lentum d | 43055 | 0.125-0.5 | Not Applicable |
a ATCC ® is the registered trademark of the American Type Culture Collection.
b reference CLSI document M100-S24 (broth dilution table 5A ; disk diffusion table 4A)
c reference CLSI document M100-S24 (broth dilution table 5B ; disk diffusion table 4B)
d reference CLSI document M11-A7 (agar dilution table 5D)
PHARMACOLOGY
Animal pharmacology
Central Nervous System
Imipenem: In female mice (5 per dose level) imipenem at doses of 6, 30 and 150 mg/kg, I.P. showed no effect on behavior or in various pharmacological tests of central nervous system activity.
In male rats (11 per dose level) imipenem at doses up to 100 mg/kg, I.V. showed no effect on spontaneous locomotor activity and had no effect on the neuromuscular junction.
No behavioral or overt signs of central nervous system activity were observed when imipenem was given to squirrel monkeys at cumulative oral doses of 1, 3 and 9 mg/kg given at 90 minute intervals (0, 90 and 180 minutes) in an avoidance response test.
The effects of imipenem on the electrocardiogram (ECG), spontaneous electroencephalogram (EEG) and the EEG arousal response in rabbits immobilized by gallamine were studied. ECG and EEG were recorded for 60 minutes following drug administration. A single dose of 50 mg/kg, I.V. of imipenem (5 animals) had no effect on either the ECG or EEG. A single I.V. dose of 200 mg/kg, (6 animals) increased the threshold voltage for EEG arousal response significantly (22.9 ± 9.5%) only at 45 minutes.
Cilastatin Sodium: Cilastatin sodium was studied in mice in the same pharmacological tests of CNS activity as used for imipenem at doses of 6, 30 and 150 mg/kg, I.P. With the exception of a possible antagonism of neurotensin hypothermia in 2 out of 5 mice given 30 mg/kg, I.P., no effects were observed.
In rats at doses up to 100 mg/kg, I.V. cilastatin sodium showed no effect on spontaneous locomotor activity and had no effect on the neuromuscular junction.
In squirrel monkeys trained on a continuous avoidance schedule, avoidance response was unaltered by cilastatin sodium at cumulative oral doses of 5, 10 and 20 mg/kg administered at 90 minute intervals (0, 90 and 180 minutes).
Imipenem/Cilastatin Sodium: Imipenem/Cilastatin sodium at doses of 25/25 and 100/100 mg/kg, I.V. induced no significant effect on central or autonomic nervous system activities in conscious mice.
The anticonvulsant activity of imipenem/cilastatin sodium was evaluated in mice on convulsions induced by electroshock, strychnine or pentylenetetrazol. At doses up to 100/100 mg/kg, I.V. no anticonvulsant effect was observed.
Imipenem/cilastatin sodium at doses up to 100/100 mg/kg, I.V. had no effect on spontaneous locomotor activity in rats. Imipenem/Cilastatin sodium at doses up to 100/100 mg/kg, I.V. had no effect on the neuromuscular junction in rats (as measured by the contractile response of the gastrocnemius muscle to electrical stimulation of the peroneal nerve).
Imipenem alone, cilastatin sodium alone and the combination (1:1 ratio) were administered intravenously to male rabbits at dosage levels of 50, 100 and 200 mg/kg to study the effect on the spontaneous electroencephalogram (EEG). Cefazolin was administered as a comparative agent at doses of 200, 400 or 1000 mg/kg. At 200 mg/kg imipenem alone caused seizure discharge in 1 of 11 rabbits 27 minutes after drug administration. This seizure discharge did not continue, but appeared again at 45 and 61 minutes. No effect on the spontaneous EEG activity was observed in the remaining 10 animals receiving 200 mg/kg of imipenem. Cilastatin had no effect on the EEG. Among rabbits receiving imipenem/cilastatin sodium at 200/200 mg/kg (the highest dose given), seizure discharge was observed in 2 of 11 rabbits from 15 minutes to 58 minutes after drug administration. Seizure discharge was observed with cefazolin at a dosage level of 400 mg/kg in 2 of 5 rabbits from 13 to 60 minutes after injection. Electrical disturbance of EEG activity was observed in all rabbits receiving cefazolin at 1000 mg/kg.
When tested in rat hippocampal slices in vitro, the GABA receptor blocking activity of imipenem was comparable to that seen with cefazolin. The GABA receptor blocking activity of imipenem/cilastatin sodium was somewhat less than that of imipenem alone. Cilastatin sodium alone had some antagonistic effect although it was significantly less than that observed with imipenem and other reference beta-lactam antibiotics.
In vivo studies in rats have shown that imipenem is convulsive after direct application of the drug into the cisterna magna. Co-administration of cilastatin sodium and imipenem in this model showed no differences in the convulsant potential compared to imipenem alone. Although direct introduction of imipenem into the rat brain is capable of producing convulsant activity, no evidence of such activity was observed in rats receiving imipenem alone at dosage levels up to 180 mg/kg/day S.C., once daily, for 6 months or with imipenem/cilastatin sodium at dosage levels up to 320/320 mg/kg/day S.C., once daily, for 6 months. In addition, no evidence of convulsant activity was observed in rhesus monkeys receiving imipenem alone, at doses up to 180 mg/kg/day I.V., once daily, for 5 weeks or imipenem/cilastatin sodium at dosage levels up to 180/180 mg/kg/day S.C., once daily, for 6 months.
Imipenem, cilastatin sodium, and the 1:1 combination were evaluated in male rabbits at dosage levels of 50 and 100 mg/kg, I.V. for their effect on the EEG arousal response. At a dosage level of 200 mg/kg, imipenem alone increased the threshold voltage by approximately 23% at 45 minutes after drug administration. Cilastatin sodium at 50 mg/kg produced a slight but statistically significant decrease in the threshold voltage for EEG arousal response. A similar slight decrease in threshold voltage was noted for the combination at a dose of 200/200 mg/kg. The reference compound for this study (diazepam, 5 mg/kg) increased the threshold voltage by 87% at 15 minutes and by 70% at 60 minutes.
Cardiovascular and Respiratory System
Imipenem: Imipenem did not significantly lower blood pressure at 20 mg/kg, I.P. in spontaneously hypertensive rats, although a slight transient increase (11%) in mean arterial blood pressure was observed two hours after treatment.
In groups of 3 dogs anesthetized with sodium pentobarbital, imipenem given intravenously at doses of 25 mg/kg and 100 mg/kg had no effect on heart rate, arterial blood pressure, respiratory rate or ECG. In one dog (dosed at 100 mg/kg) heart rate increased by about 25 beats/min (21%) and systolic blood pressure increased about 16 mmHg (12%). In respiratory studies in dogs anesthetized with thiopental, imipenem at doses of 2.5 and 10 mg/kg, I.V. had no effect on the respiratory parameters measured (total lung resistance, dynamic lung compliance, tidal volume and respiratory rate).
Cilastatin Sodium: No appreciable change in basal blood pressure or heart rate was observed in spontaneously hypertensive rats or dogs dosed with cilastatin sodium at 10 mg/kg, I.V.
Cilastatin sodium at doses up to 100 mg/kg, I.V. did not change blood pressure, heart rate, respiratory rate and ECG in dogs anesthetized with sodium pentobarbital.
Imipenem/Cilastatin sodium: At doses of 25/25 and 100/100 mg/kg, I.V. imipenem/cilastatin sodium significantly (p < 0.05) inhibited the carotid sinus reflexes (24.5% and 36% respectively) in dogs anesthetized with sodium pentobarbital.
In other studies in dogs anesthetized with sodium pentobarbital, a dose of imipenem/cilastatin sodium 100/100 mg/k g, I.V. decreased mean blood pressure (7 to 13 mmHg) within 4 to 15 minutes after the start of drug infusion, without any significant change in heart rate and respiration rate. This may have been related to the inhibition of the carotid sinus reflexes observed in the previous study. A dose of 25/25 mg/kg, I.V. did not affect these parameters.
Other Systems
Imipenem: In mice (male, 8 per dosage level), imipenem administered subcutaneously at doses of 2.5 to 20 mg/kg or intravenously at doses of 25 and 100 mg/kg had no effect on the intestinal propulsion rate.
No diuretic activity was observed in rats given imipenem at doses up to 10 mg/kg, I.P. or in dogs given 5 mg/kg, I.V.
In seven female dogs, gastric secretion evoked by gastrin tetrapeptide resulted in total acid output at the 0 - to 30-minute collection which was significantly reduced (59%, p < 0.05) following an oral dose of imipenem of 20 mg/kg. This was related to a reduction in output volume. The integrated 0 - to 90-minute total acid output and output volume did not differ significantly (p > 0.05) from those in a placebo trial in the same animals. Acid concentration was not affected by imipenem. Basal gastric secretion in dogs was not affected following oral doses of 10 or 20 mg/kg of imipenem.
Cilastatin Sodium: In pylorus-ligated rats, cilastatin sodium (25 and 100 mg/kg, I.V.) showed no effect on basal gastric output, acid output, pH and pepsin output.
Cilastatin sodium (25 and 100 mg/kg, I.V.) showed no effect on intestinal propulsion in male mice.
Cilastatin sodium (10 mg/kg, I.V.) did not substantially change urinary Na +, K + or Ca ++ excretion in beagle dogs.
In female dogs, cilastatin sodium (10 mg/kg, I.V.) did not significantly alter the response to gastrin tetrapeptide. Basal gastric output was reduced but not to a statistically significant degree.
Imipenem/Cilastatin sodium: Imipenem/Cilastatin sodium at doses of 25/25 and 100/100 mg/kg, I.V. had no effect on basal gastric secretion in pylorus-ligated rats. In mice, imipenem/cilastatin sodium (25/25 and 100/100 mg/kg, I.V.) had no effect on intestinal propulsion.
Metabolism and Excretion
During the laboratory evaluation of imipenem as a single entity, low urinary recovery of the antibiotic was found in the mouse (26%), rabbit (51%), dog (8%), Rhesus monkey (41%) and the chimpanzee (13%), and this was subsequently confirmed in man. Metabolism was shown to occur primarily in the kidney, affecting the secreted and filtered fraction of the antibiotic after its clearance from the blood.
The major pathway of metabolism of imipenem is by hydrolysis of the beta-lactam ring by the enzyme known as dehydropeptidase-I localized on the luminal (brush-border) surface of the proximal renal tubular epithelium. This enzyme has access to the antibiotic both in the glomerular filtrate and during the transcellular secretory process.
This low urinary tract bioavailability of imipenem is avoided by co-administration of cilastatin sodium, a potent inhibitor of dehydropeptidase-I.
The inhibition of dehydropeptidase-I by Cilastatin sodium is competitive and freely reversible. Cilastatin sodium has been shown not to inhibit the activity of four other zinc metalloenzyme peptidases, including angiotensin converting enzyme. Cilastatin sodium is devoid of antimicrobial activity per se, and has no effect on the antimicrobial activity of imipenem.
Human Pharmacology
Pharmacokinetics
Imipenem and cilastatin sodium for injection was administered via intravenous infusion over 20 minutes at a single dose of 250/250 mg to 4 male subjects (mean age: 31.5 ± 0.6 years), at a single dose of 500/500 mg to 20 male subjects (mean age: 26.8 ± 4.1 years), and at a single dose of 1000/1000 mg to 8 male subjects (mean age: 24.8 ± 3.7 years). Peak plasma levels of imipenem and of cilastatin were measured at the end of a 20 minute infusion, and are presented in Table 5. Plasma levels of imipenem antimicrobial activity are proportional to the dose and decline to below 1 µg /mL or less in 4 to 6 hours.
TABLE 5: RANGE OF PEAK PLASMA LEVELS OF IMIPENEM AND CILASTATIN
FOLLOWING A 20 MINUTE I.V. INFUSION OF IMIPENEM AND CILASTATIN SODIUM FOR INJECTION
| 250/250 mg | 500/500 mg | 1000/1000 mg | |
|---|---|---|---|
| Imipenem ( µg/mL) | 12 - 20 | 21 - 58 | 41 - 83 |
| Cilastatin (µg /mL) | 21 - 26 | 21 - 55 | 56 - 88 |
Imipenem and cilastatin sodium for injection was administered via the intravenous route, over a 30 minute period, every 6 hours, for a period of 10 days, at a dose of 1000/1000 mg, to a group of six male volunteers (mean age 28.2 ± 5.0).
Mean plasma and urine concentrations for imipenem are given in Figure 1 and Table 6 respectively.
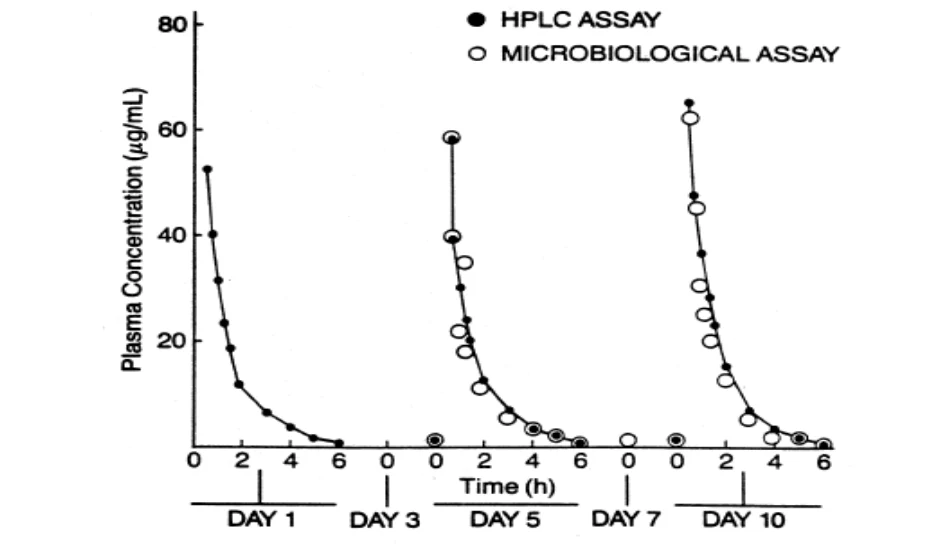
FIGURE 1
MEAN IMIPENEM PLASMA CONCENTRATION PROFILES WHEN IMIPENEM AND CILASTATIN SODIUM FOR INJECTION IS ADMINISTERED AT A DOSE OF1000/1000 mg, BY I.V. INFUSION, OVER 30 min (every 6 h) (n = 6)
TABLE 6: MEAN IMIPENEM URINE CONCENTRATIONS (µg /mL ± S.D.) WHEN IMIPENEM AND CILASTATIN SODIUM FOR INJECTION IS ADMINISTERED AT A DOSE OF 1000/1000 mg BY I.V. INFUSION, OVER 30 min (every 6 h)
| 0 - 2 h | 2 - 4 h | 4 - 6 h | |
|---|---|---|---|
| Day 1 | 886.6 (±511.3) | 562.8 (±269.3) | 175.8 (±167.9) |
| Day 5 | 1026.1 (±503.9) | 1185.8 (±932.4) | 156.1 (± 93.77) |
| Day 10 | 1389.5 (±616.4) | 891.5 (±430.6) | 159.9 (± 49.1) |
The pharmacokinetic parameters for imipenem and cilastatin, when imipenem and cilastatin sodium for injection are administered at a dose of 1000/1000 mg, are summarized in Table 7.
TABLE 7: PHARMACOKINETIC PARAMETERS OF IMIPENEM AND CILASTATIN WHEN IMIPENEM AND CILASTATIN SODIUM FOR INJECTION IS ADMINISTERED AT A DOSE OF 1000/1000 mg BY I.V. INFUSION OVER 30 MIN (N = 6)
| Time (days) | Volume of Distribution (L) | Area under the Plasma Concentration Time Curve Between 0 and 6 h ( µg.h/mL) | Plasma Half-Lives (min)* | Dose Recovered in urine through 6 h (mg) | Cumulative Renal Clearance (mL/min) | Plasma Clearance (mL/min) | |||
|---|---|---|---|---|---|---|---|---|---|
| IMIPENEM | |||||||||
| Day 1 | 13.6 (±3.7) | 73.3 (±10.4) | 59.6 | 540.2 (±54.1) | 126.5 (±29.9) | 227.7 (±30.9) | |||
| Day 5 | 11.4 (±3.8) | 74.5 (±10.9) | 61.3 | 651.8 (±148.1) | 139.9 (±27.4) | 227.8 (±36.1) | |||
| Day 10 | 10.9 (±1.6) | 79.7 (±7.1) | 59.4 | 626.5 (±77.2) | 131.3 (±21.0) | 210.4 (±18.3) | |||
| CILASTATIN | |||||||||
| Day 1 | 10.3 (±3.9) | 82.1 (±19.3) | 57.5 | 698.6 (±33.9) | 142.7 (±33.6) | 208.9 (±43.0) | |||
| Day 5 | 9.5 (±1.4) | 73.0 (±16.1) | 50.7 | ND | ND | 236.5 (±44.9) | |||
| Day 10 | 9.7 (±2.1) | 77.4 (±15.1) | 50.8 | ND | ND | 221.6 (±38.6) | |||
*Harmonic means
Excretion and Metabolism: Imipenem, when administered alone, is metabolized in the kidneys by dehydropeptidase-I and therefore achieves relatively low levels in urine.
Cilastatin sodium is a specific inhibitor of this enzyme and it prevents renal metabolism of imipenem. When imipenem and cilastatin sodium are given concomitantly, approximately 70% of the administered imipenem and cilastatin sodium are recovered unchanged in the urine within 10 hours of administration, after which no further urinary excretion is detectable. Urine concentrations of imipenem in excess of 10 µg/mL can be maintained for up to 8 hours with imipenem and cilastatin sodium for injection at the 500 mg dose.
The remainder of the administered dose of imipenem is recovered in the urine as antibacterially inactive metabolites and fecal elimination of imipenem is essentially nil.
Approximately 10% of the cilastatin sodium administered is found as the N-acetyl metabolite, which has inhibitory activity against dehydropeptidase comparable to that of the parent drug. Activity of dehydropeptidase-I in the kidney returns to normal levels within approximately 8-12 hours after the elimination of cilastatin from the bloodstream.
No accumulation of imipenem and cilastatin in plasma is observed with regimens of imipenem and cilastatin sodium for injection administered at therapeutic doses, in patients with normal renal function.
Serum Protein Binding: At serum concentration of 25 mg/L, the human serum protein binding of imipenem is 20%. Cilastatin sodium binding to protein was found to be approximately 35% in the human serum.
Tissue Concentrations: Concurrent imipenem concentrations in serum, tissues and body fluids are given in Table 8.
TABLE 8: IMIPENEM CONCENTRATIONS IN HUMAN TISSUES AFTER ADMINISTRATION BY I.V. INFUSION
| Tissue/Fluid | Dose of Imipenem (mg) | Sampling time (min after dose) | No. of Specimens | Concentration | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Tissue/Fluid (mg/L or mg/kg) | Serum (mg/L) | |||||||||||||||||
| Bile (1) | 500 1000 | 20 180 20 180 | 9 8 | MEAN MAX (RANGE) 12.5 (5.25 - 20.3) >1 (0.46 - 2.73) 25.0 (10.7 - 51.28) (1.45 - 4.12) | - - - - | |||||||||||||
| Cerebrospinal (2) | 1000 | 60 90 120 | 4 | MEAN ± S.D. 2.0 (±1.3) 1.5 (±0.1) 2.7 (±2.3) | MEAN ± S.D.(n=4) 22.3 (±14.6) 8.0 (± 1.6) 13.9 (±14.4) | |||||||||||||
Saliva (3) Sputum (3) Bone (3) Wound Drainage (3) Gastric Fluid (3) | 1000 1000 1000 1000 1000 | 15 - 60 15 - 120 30 - 120 15 - 120 15 - 90 | 10 7 10 9 6 | MEAN(RANGE) 0.38 (0.3 - 0.6) 4.4 (2.1 - 10.4) 2.6 (0.4 - 5.4) 7.2 (1.7 - 22.6) 0.9 (0.4 - 1.7) | MEAN PEAK±S.D.** 34.9 (±4.0) (n=32) | |||||||||||||
Heart Valves (4) Fat (4) Muscle (4) | 1000 1000 1000 | 0 - 60 0 - 60 0 - 60 | 3 10 10 | MEAN ± S.E. 3.3 (±0.7) 0.8 (±0.3) 2.5 (±0.7) | MEAN ± S.E. 47.2 (±4.7) (n=16) | |||||||||||||
Myometrium (4) Endometrium (4) Salpinges (4) | 500 500 500 | 60 - 120 60 - 120 60 - 1205 | 5 5 2 | 2.5 (±0.3) 1.6 (±0.3) 1.4 (±0.1) | 14.6 (±1.6) (n=5) | |||||||||||||
** 15 min post infusion
(1) Mayer M, Tophoff C, Opperkuch W. Bile levels of imipenem following different dose regimens. Int J Clin Pharmacol Res 1985; V(5):325-9.
(2) Modal J, Vittecoq D, Decazes JM, Meulemans A. Penetration of imipenem and cilastatin into cerebrospinal fluid of patients with bacterial meningitis. J Antimicrob Chemother 1985; 16: 751-5.
(3) MacGregor RR, Gibson GA, Bland JA. Imipenem pharmacokinetics and body fluid concentrations in patients receiving high-dose treatment of serious infections. Antimicrob Agents Chemother 1986; 29(2):188-92.
(4) Kümmel A, Schlosser V, Petersen E, Daschner FD. Pharmacokinetics of imipenem-cilastatin in serum and tissue. Eur J Clin Microbiol 1985; 4(6):609-10.
Factors influencing pharmacokinetics
Age
Children: The pharmacokinetic results from two pediatric single dose studies are summarized in Table 9.
TABLE 9: MEAN VALUES OF PHARMACOKINETIC PARAMETERS OF IMIPENEM/CILASTATIN IN CHILDREN AFTER A SINGLE DOSE OF IMIPENEM AND CILASTATIN SODIUM FOR INJECTION (10/10 or 25/25 mg/kg) ADMINISTERED I.V. OVER 10-20 min
| AGE RANGE (years) | No. PATIENTS | [AUC * ] (µg.h/mL/mg) | PLASMA CLEARANCE (mL/min/kg) | VOLUME OF DISTRIBUTION (L/kg) | T½ + (min) | URINE RECOVERY (% OF DOSE) |
|---|---|---|---|---|---|---|
| 2-12 | 20T | 0.20 / 0.29 (n=9)/(n=3) | 5.33 / 4.20 (n=9)/(n=3) | 0.25 / 0.17 (n=9)/(n=3) | 55.8 / 36.5 (n=20)/(n=10) | 61.0 / 79.0 (n=7)/(n=5) |
| 2- 9 | 9 | 0.18 / 0.20 | 5.40 / 4.90 | 0.22 / 0.15 | 53.7 / 37.9 | 41.0 / 66.0 |
* AUC expressed per milligram of drug administered.
+ Harmonic means.
Ϯ Number of patients from which pharmacokinetic parameters were calculated are given in between parentheses.
The pharmacokinetic results from two pediatric studies in which imipenem and cilastatin sodium for injection was administered in multiple doses are summarized in Table 10. Imipenem and cilastatin sodium for injection was administered at a dose of 25/25 mg/kg/q6 h for patients aged 3 months to <3 years and at a dose of 15/15 mg/kg/q6 h for patients aged 3 to 12 years.
TABLE 10: MEAN VALUES OF PHARMACOKINETIC PARAMETERS OF IMIPENEM/CILASTATIN IN CHILDREN AFTER MULTIPLE DOSES
| TOTAL No. PTS | AGE RANGE (yrs) | TOTAL AUC XX (µg.h/mL/mg)** | PLASMA CLEARANCE (mL/min/kg)** | VOLUME OF DISTRIBUTION (L/kg)** | RENAL CLEARANCE (mL/min) | T ½ + (min) | DOSING INTERVAL UINARY RECOVERY (% OF DOSE) |
|---|---|---|---|---|---|---|---|
| 106 † | 1 ≤ 3 3 ≤ 6 6 ≤ 9 9 ≤ 12 | 0.18/ x (n=1)/- 0.08/ x (n=1)/- 0.10/ x (n=1)/- 0.07/ x (n=3)/- | 6.9/ x (n=1)/- 12.7/ x (n=1)/- 6.4/ x (n=1)/- 6.0/ x (n=3)/- | 0.23/ x (n=1)/- 0.55/ x (n=1)/- 0.33/ x (n=1)/- 0.24/ x (n=3)/- | 59/ x (n=1)/- 85/ x (n=1)/- 100/ x (n=1)/- 118 to 161/ x (n=3)/- | 67.9/ x (n=1)/- 60.0/ x (n=2)/- 54.7/ x (n=1)/- 52.3/ x (n=3)/- | 63.5/78.6 (n=1)/(n=1) 39.4/61.7 (n=1)/(n=1) 57.0/71.3 (n=1)/(n=1) 53.0/65.6 (n=4)/(n=4) |
| 178 † | ≤ 1 1 ≤ 3 3 ≤ 6 6 ≤ 9 9 ≤ 12 | 0.42/0.34 (n=10)/(n=3) 0.40/0.41 (n=10)/(n=3) 0.19/0.24 (n=7)/(n=2) 0.14/ x (n=7)/- 0.17/0.22 (n=4)/(n=2) | 5.1/5.3 (n=10)/(n=3) 3.8/4.0 (n=6)/(n=3) 5.2/5.4 (n=7)/(n=2) 4.7/ x (n=7)/- 4.4/4.4 (n=4)/(n=2) | 0.30/0.19 (n=10)/(n=3) 0.14/0.11 (n=6)/(n=3) 0.22/0.13 (n=7)/(n=1) 0.21/ x (n=7)/- 0.22/0.13 (n=4)/(n=2) | 20 to 47/ 37 to 64 (n=6)/(n=3) 32 to 51/ 54 to 57 (n=5)/(n=2) 48 to 99/44 (n=6)/(n=1) 53 to 116/ x (n=4)/- 28 to 124/ 37 to 87 (n=2)/(n=2) | 58.0/59.0 (n=10)/(n=3) 52.0/41.0 (n=6)/(n=3) 48.0/23.0 (n=7)/(n=2) 55.0/ x (n=7)/- 73.0/39.0 (n=4)/(n=2) | ≥44/ ≥67 xxx (n=6)/(n=5) ≥77/ ≥73 xxx (n=5)/(n=4) ≥73/ ≥51 xxx (n=6)/(n=5) ≥63/ ≥89 xxx (n=4)/(n=2) ≥75/ ≥64 xxx (n=2)/(n=2) |
** Geometric means
+ Harmonic means
†Number of patients evaluated pharmacokinetically is indicated in parentheses
x Insufficient data
xx Dosing interval AUC (0-6h) expressed per mg of drug administered
xxx Means not provided
Representative plasma concentration profiles of imipenem and cilastatin at doses of 15/15 and 25/25 mg/kg are shown in Figure 2. In these studies, plasma concentrations of Cilastatin were below detectable limits three hours postdosing. Steady state conditions for imipenem and cilastatin prevailed before the end of the fourth dose on Day 1.
Because of the short half-lives of imipenem and cilastatin, no accumulation was observed when imipenem and cilastatin sodium for injection were given every 6 hours. As in the single dose pediatric studies, the disposition of imipenem and cilastatin resembled that of adults, except for a greater rate of cilastatin elimination.
Imipenem Plasma Concentration
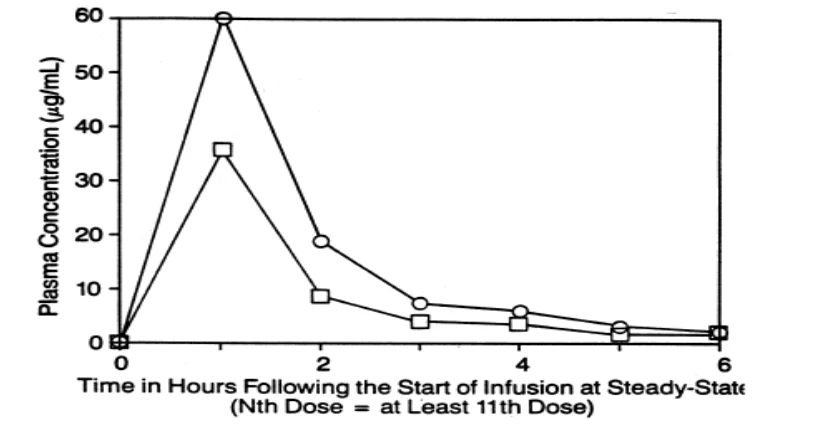
□ 15mg/kg = 12 Patients
- 25mg/kg = 13 Patients
Cilastatin Plasma Concentration
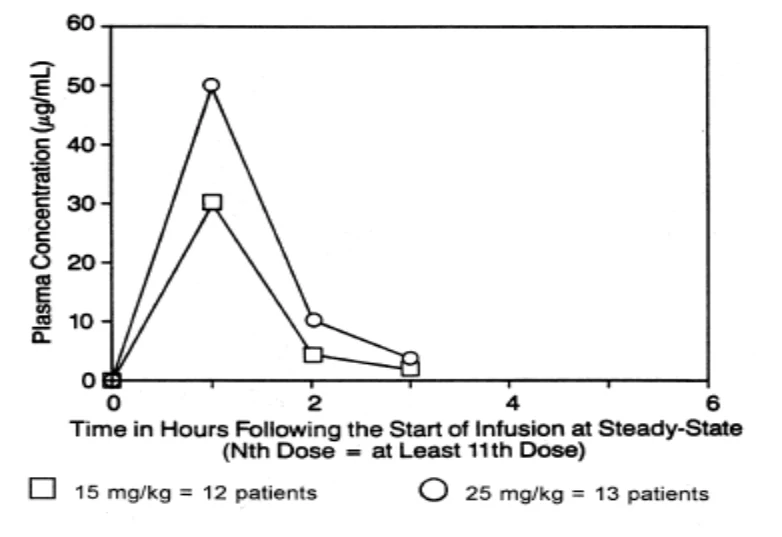
FIGURE 2: Representative Mean Steady-State Plasma Concentrations of Imipenem and Cilastatin in Pediatric Patients Receiving Imipenem/Cilastatin Sodium Every Six Hours
Elderly: In 4 female and 2 male healthy volunteers, 65 to 75 years old (mean age 68.8) with normal renal function for their age, i.e., creatinine clearance 84.3 (±13.0) mL/min/1.73 m2 (1.41(±0.2) mL/s/1.73 m2), imipenem and cilastatin sodium for injection were administered by intravenous infusion at a dose of 500/500 mg in 100 mL saline over a period of 20 minutes.
The pharmacokinetic parameters for imipenem and cilastatin are summarized in Table 11.
TABLE 11: PHARMACOKINETIC PARAMETERS FOR IMIPENEM AND CILASTATIN IN THE ELDERLY (SINGLE DOSE OF 500/500 mg BY I.V. INFUSION OVER 20 min)
| IMIPENEM | CILASTATIN | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| PARAMETER | MEAN (±S.D.) | RANGE | MEAN (±S.D.) | RANGE | |||||||||
Total urinary recovery (% dose) | 58 ± 7 | 49 - 66 | 69 ± 11 | 49 - 80 | |||||||||
Renal clearance (mL/min) | 79 ± 11 | 67 - 95 | 98 ± 26 | 64 - 133 | |||||||||
Plasma clearance (mL/min) | 132 ± 10 | 122 - 147 | 142 ± 22 | 117 - 171 | |||||||||
| Total AUC ( µg . h/mL) | 64 ± 5 | 57 - 68 | 60 ± 9.1 | 49 - 71 | |||||||||
| Plasma half-life (min) | 90 + | 84 - 102 | 66 + | 54 - 96 | |||||||||
+ Harmonic means
No dosage adjustment is necessary for elderly patients whose degree of renal function is normal for their age.
Impaired Renal Function
Imipenem and cilastatin sodium for injection was administered to six healthy male volunteers and 25 patients with different degrees of renal impairment at a dose of 250/250 mg, in single I.V. infusions over 5 minutes.
The pharmacokinetic parameters for imipenem and cilastatin are summarized in Table 12 and the plasma concentration profiles are shown in Figures 3 and 4 respectively.
TABLE 12: PHARMACOKINETIC PARAMETERS FOR IMIPENEM AND CILASTATIN IN PATIENTS WITH RENAL FAILURE (SINGLE DOSE OF 250/250 mg BY I.V. INFUSION OVER 5 min)
| GROUP No. | No. PTS | MEAN AGE (yrs) | CREATININE CLEARANCE mL/min/1.73 m2 (mL/s/1.73 m2 ) | % DOSE URINARY RECOVERY | RENAL CLEARANCE (mL/min) | PLASMA CLEARANCE (mL/min) | [AUC]x µg .h/mL | T1/2xx (min) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| IMIPENEM | ||||||||||||||||
I II III IV V a V b | 6 6 9 2 4 4 | 22.8 41.8 50.8 32&67 42.3 61.5 | >100 (>1.7) 31-99 (0.52-1.65) 10-30 (0.17-0.50) <10 (<0.17) Hemodialysis† Hemodialysis†† | 46.2 51.0 y 26.1zz 11.3 3.4 | 101.9 77.7 y 24.2zz 8.5 1.8 | 219.5 157.2 86.2 69.3 184.0 59.1 | 19.8 30.3 51.6 60.6 23.1 73.1 | 56 92 139 160 74 181 | ||||||||
| CILASTATIN | ||||||||||||||||
I II III IV V a V b | 6 6 9 2 4 4 | 22.8 41.8 50.8 32&67 42.3 61.5 | >100 (>1.7) 31-99 (0.52-1.65) 10-30 (0.17-0.50) <10 (<0.17) Hemodialysis† Hemodialysis†† | 59.4 71.2 y 61.9 z 39.4 17.9 | 100.7 71.3 y 23.9 zz 6.5 2.0 | 168.5 99.9 38.4 16.2 74.9 11.4 | 25.4 45.7 135.3 261.4 56.7 416.8 | 54 84 198 462 132 696 | ||||||||
† Received dose during hemodialysis
†† Measurements done between dialysis sessions
x AUC normalised to a 250 mg dose
xx Harmonic means
y n = 5
z n = 6
zz n = 8
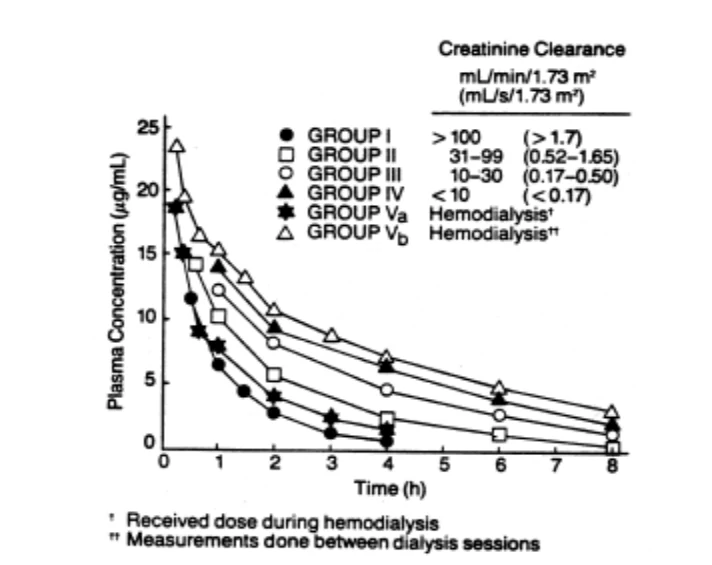
FIGURE 3: MEAN IMIPENEM PLASMA CONCENTRATIONS FOLLOWING A SINGLE-DOSE OF IMIPENEM AND CILASTATIN SODIUM FOR INJECTION (250/250 mg I.V., OVER 5 min) TO SUBJECTS WITH VARYING DEGREES OF RENAL INSUFFICIENCY.
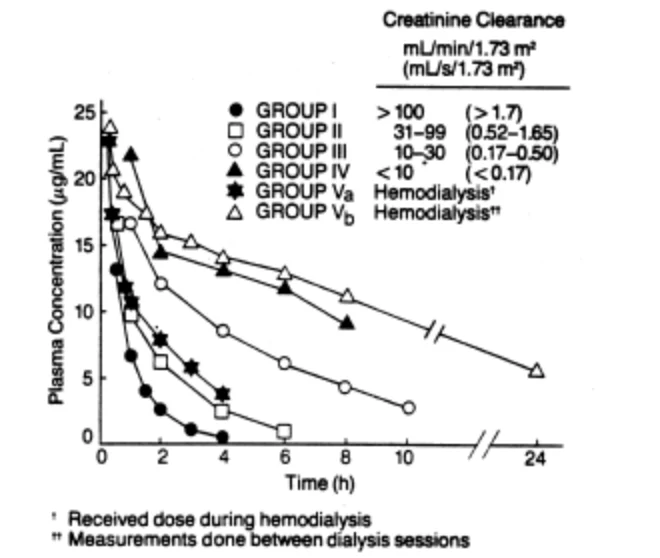
FIGURE 4: MEAN CILASTATIN PLASMA CONCENTRATIONS FOLLOWING A SINGLE-DOSE OF IMIPENEM AND CILASTATIN SODIUM FOR INJECTION (250/250 mg I.V., OVER 5 min) TO SUBJECTS WITH VARYING DEGREES OF RENAL INSUFFICIENCY.
Imipenem and cilastatin sodium for injection was administered to 15 hospitalized patients (age range: 39-72 years) with proven or suspected urinary infection, at a dose of 500/500 mg by I.V. infusion over 20 minutes, repeated every 6 hours, for 3 to 10 days.
The pharmacokinetic parameters for imipenem and cilastatin are summarized in Table 13.
Repeated administration did not alter the disposition of either imipenem or cilastatin from that observed after a single dose and steady state prevailed by the end of first day dosing.
TABLE 13: PHARMACOKINETIC PARAMETERS FOR IMIPENEM AND CILASTATIN WHEN IMIPENEM AND CILASTATIN SODIUM FOR INJECTION WAS ADMINISTERED AT 500/500 mg BY I.V. INFUSION OVER 20 min - EVERY 6 h
| GROUP DOSE | URINARY RECOVERY 0 - 6 h(mg) | RENAL CLEARANCE | PLASMA CLEARANCE | [AUC]0 - 6 h | T1/2x (min) |
|---|---|---|---|---|---|
| (mL/min) | (mL/min) | ( µg.h/mL) | |||
IMIPENEM
Ia 1st 250.1 (± 45.5) 105.1 (±39.0) 201.2 (±63.8) 42.9(±10.7) 80 n = 9 n = 9 n = 9 n = 9 n = 9 Nth 287.0 (±100.7) 128.3 (±69.1) 222.5 (±46.8) 39.1 (± 8.9) 72 n = 8 n = 8 n = 8 n = 8 n = 9 IIb 1st 183.5 (± 39.8) 69.3 (±14.0) 167.0 (±50.9) 50.7(±16.8) 98 n=4 n=4 n=5 n=5 n=5 Nth 231.5 (± 40.3) 87.8 (±26.2) 175.7 (±49.5) 51.0(±15.9) 100 n=4 n=4 n=5 n=5 n=5 |
|---|
CILASTATIN
Ia 1st 342.1 (± 70.6) 122.5 (±22.7) 214.7 (±59.3) 40.9(±11.8) 57 n = 3 n = 3 n = 9 n = 9 n = 9 Nth 258.7 (± 73.6) 100.8 (±26.2) 222.6 (±60.2) 222.6 (±60.2) 55 n = 3 n = 3 n = 8 n = 8 n = 9 IIb 1st 204.6 50.3 148.6 (±60.4) 59.6(±23.9) 92 n = 1 n = 1 n = 6 n = 6 n = 6 Nth 224.9 (± 59.6) 71.8 (±26.6) 158.8 (±60.8) 60.7(±27.1) 86 n = 2 n = 2 n = 6 n = 6 n = 6 |
|---|
a Group I = glomerular filtration rate ≥100 mL/min/1.73 m2 (1.667 mL/s/1.73 m2) and N ≥ 16 doses.
b Group II = glomerular filtration rate ≤ 100 mL/min/1.73 m2 (1.667 mL/s/1.73 m2) but ≥50 mL/min/1.73 m2 (0.834 mL/s/1.73 m2) and N ≥ 15 doses.
x Harmonic means.
Six hospitalized patients (4 females, 2 males, mean age 52.3) with a glomerular filtration rate of less than 15 mL/min/1.73 m2 (0.25 mL/s/1.73 m2) but not requiring hemodialysis, were administered imipenem and cilastatin sodium for injection at a dose of 500/500 mg by I.V. infusion over 20 minutes, every 12 hours for nine doses.
The pharmacokinetic parameter estimates are summarized in Table 14.
TABLE 14: PHARMACOKINETIC PARAMETER ESTIMATES IN PATIENTS WITH SEVERELY IMPAIRED RENAL FUNCTION
| DOSE No. | IMIPENEM MEAN | CILASTATIN MEAN | |
|---|---|---|---|
Urinary recovery (% administered dose) | 1 9 | 15.2 13.8 (1.2) | 38.0 46.7x (6.5) |
| Renal clearance (mL/min) | 1 9 | 7.8 7.1x (0.6) | 10.4 9.1 (1.6) |
| Plasma clearance (mL/min) | 1 9 | 51 54xxx (1.2) | 21 19 (1.9) |
12-hour AUC ( µg hr/mL) | 1 9 | 158 159 (4.3) | 313 431xxx (33) |
| Plasma half-life a (h) | 1 9 | 2.9 2.6xx | 5.7 5.5 |
x Different from Dose 1, .05 < p ≤.10 xx Different from Dose 1, .01 < p ≤.05 xxx Different from Dose 1, p≤ .01 a Inverse (harmonic) transformed data
Numbers in parentheses are within patient standard deviations.
Probenecid
In twelve male volunteers (mean age 29.5, range 23-37) imipenem and cilastatin sodium for injection was administered at a dose of 500/500 mg with and without probenecid (1 g orally at ten hours and one hour prior to treatment). The urinary recovery of imipenem and cilastatin and their pharmacokinetic data are given in Table 15.
TABLE 15: EFFECT OF PROBENECID ON THE PHARMACOKINETICS AND URINARY RECOVERY OF IMIPENEM AND CILASTATIN WHEN IMIPENEM/CILASTATIN SODIUM (500/500 mg) WAS ADMINISTERED
| IMIPENEM/ CILASTATIN SODIUM | IMIPENEM/CILASTATIN SODIUM PLUS PROBENECID | |
|---|---|---|
| Imipenem | ||
| Plasma clearance (mL/min) | 185 (± 32)x | 159 (± 24) |
| AUC (µg.h/mL) | 46 (± 7) | 53 (± 8) |
| Plasma half-life (min)xx | 58 | 66 |
| Urinary recovery (% dose) | 66 (± 3) | 55 (± 6) |
| Renal clearance (mL/min) | 125 (± 20) | 88 (± 17) |
| Cilastatin | ||
| Plasma clearance (mL/min) | 218 (± 39) | 89 (± 10) |
| AUC (µg.h/mL) | 39 (± 7) | 95 (± 11) |
| Plasma half-life (min)xx | 48 | 102 |
| Urinary recovery (% dose) | 75 (± 6) | 75 (± 8) |
| Renal clearance (mL/min) | 173 (± 31) | 70 (± 9) |
x Mean (±S.D.)
xx Harmonic means
TOXICOLOGY
Acute Toxicity
| LD50 | ||||||
|---|---|---|---|---|---|---|
| RAT | MOUSE | |||||
| Imipenem I.V. | >2000 mg/kg | ≈ 1500 mg/kg | ||||
| Cilastatin Sodium I.V. | ≈ 5000 mg/kg | ≈8709 mg/kg | ||||
| Imipenem and cilastatin sodium for injection I.V. | ≈ 1000 mg/kg | ≈1100 mg/kg | ||||
Sub-acute and Chronic Toxicity
Imipenem: The principal studies used to evaluate the subacute and chronic toxicity of the product are shown in Table 16.
Animal studies showed that the toxicity produced by imipenem as a single entity, was limited to the kidney. Nephrotoxicity (characterized by proximal tubular necrosis) was observed in rabbits and monkeys receiving high doses of imipenem (150 mg/kg, I.V. and 180 mg/kg, I.V. respectively); the rabbit is more sensitive to the nephrotoxic effect of imipenem than is the monkey. No adverse effects were observed after 6 months of administration of imipenem in rats (25 males and 25 females per dosage level), at dosage levels up to 180 mg/kg/day, or in monkeys (5 males and 5 females per dosage level) at dosage levels up to 120 mg/kg/day.
TABLE 16
PRINCIPAL SUBACUTE AND CHRONIC TOXICITY STUDIES WITH IMIPENEM AND CILASTATIN SODIUM FOR INJECTION1
| Duration | Species, Number/ Sex/Group | Dosage Levels (mg/kg/day) | No Adverse Effect Level (mg/kg/day) | Principal Effects Observed | |||||
|---|---|---|---|---|---|---|---|---|---|
| Studies with Imipenem Alone | |||||||||
| 5-week IV | Rat 15 | 20, 60, 180 | 180 | No adverse effect observed | |||||
| 5-week IV | Monkey 3M, 3F | 20, 60, 180 | 60 | 1/6 dead with renal tubular necrosis at 180; an additional death from unknown cause at 180 presumed related to injection of highly concentrated drug solution necessitated by dosage level. | |||||
| 6-month IV (w/3-mo interim necropsy | Rat 25 (10 for interim necropsy) | 20, 60, 180 | 180 | Increased rate of weight gain in males at 60 and 180; no adverse effects seen. | |||||
| 6-month IV S.C (w/3-mo interim necropsy | Monkey 5 (2 for interim necropsy) | 30 , 60 IV 120 S.C | 120 | No adverse systemic effects seen. | |||||
| Studies with Cilastatin Alone | |||||||||
| 5-week IV | Rat, 15 | 20, 100, 500 | 500 | No adverse effect seen. | |||||
| 5-week S.C | Rat, 15 | 500, 1250, 3125 | 500 | Renal tubular vacuolation seen at 1250 and 3125. | |||||
| 5-week IV | Monkey, 3 | 20, 100, 500 | 500 | No drug-induced adverse effects. | |||||
| 14-week IV | Rat, 15 | 20, 100, 500 | 500 | No changes related to treatment. | |||||
1 Although many studies in addition to those listed here were conducted, this list presents the principal studies which formed the basis of the safety evaluation of this drug.
TABLE 16
PRINCIPAL SUBACUTE AND CHRONIC TOXICITY STUDIES WITH IMIPENEM & CILASTATIN FOR INJECTION USP (continued)
| Duration | Species, Number/ Sex/Group | Dosage Levels (mg/kg/day) | No Adverse Effect Level (mg/kg/day) | Principal Effects Observed | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Studies with Imipenem & Cilastatin Sodium in Combination (Imipenem and cilastatin sodium for injection) | |||||||||||
| 5-week, I.V., S.C | Rat, 15 | 20/20, 80/80 I.V. 320/320 S.C | 320/320 | No drug-induced adverse effects. | |||||||
| 5-week, I.V., S.C | Monkey, 3 | 20/20, 60/60 I.V. 180/180 S.C | 180/180 | No changes related to treatment. | |||||||
| 14-week, I.V., S.C | Rat, 15 | 20/20, 80/80, 320/320 | 320/320 | No changes related to treatment. | |||||||
| 14-week ,S.C | Infant Monkey, 3 | 20/20, 60/60, 180/180 | 180/180 | No adverse drug-induced changes. | |||||||
| 10 –Week, S.C | Newborn Monkey, 5M, 3F | 180/180 | 180/180 | No drug-induced adverse effects. | |||||||
| 6-Month, I.V., S.C | Rat,30 | 20/20, 80/80 I.V. 320/320 S.C | 320/320 | No adverse effects observed. | |||||||
| 6-Month, I.V., S.C | Monkey, 4 | 20/20, 60/60 I.V., 180/180 S.C | 180/180 | No adverse effects observed. | |||||||
Cilastatin Sodium: No adverse effects were noted after intravenous administration of cilastatin sodium to rats (15 males and 15 females per dosage level) at doses up to 500 mg/kg for 14 weeks and monkeys (3 males and 3 females per dosage level) at doses up to 500 mg/kg for five weeks. In rats (15 males and 15 females per dosage level) given cilastatin sodium at dosages of 1250 or 3125 mg/kg/day, subcutaneously, very slight to slight proximal renal tubular degeneration was observed. After 5 weeks on these doses, no tubular necrosis was found, and there were no changes in any other tissues. Renal function remained normal.
Imipenem/Cilastatin Sodium: Co-administration of cilastatin sodium with imipenem in a 1:1 ratio prevented the nephrotoxic effects of Imipenem in rabbits and monkeys, even when the dose of imipenem was 360 mg/kg or 180 mg/kg/day, respectively. These dosage levels are nephrotoxic when administered without cilastatin. This protective effect was seen in the monkey through 6 months of co-administration.
A series of studies performed in rabbits demonstrated that cilastatin sodium prevents the nephrotoxicity of imipenem in animals by preventing its entry into the tubular cells; this action is apparently distinct from the inhibition by administration of dehydropeptidase-I.
Reproduction studies
The principal studies performed to evaluate the effect of imipenem or cilastatin sodium alone or in combination on reproductive parameters or fetal development are shown in Table 17.
Fertility
The effect of imipenem/cilastatin sodium on fertility was assessed in male and female rats administered doses up to 320/320 mg/kg/day. Drug was administered to males for 12 weeks prior to mating and throughout the mating period. Females received drug beginning 15 days prior to mating, during mating and through Day 19 of gestation.
The only effect of imipenem/cilastatin sodium in these studies was a very slight but statistically significant embryotoxicity and/or fetotoxicity. This was expressed as an increase in the resorption rate among animals receiving 80/80 and 320/320 mg/kg/day as well as a decrease in the number of live fetuses per pregnant female at 20/20 and 80/80 mg/kg/day. No decrease in the number of live fetuses per pregnant female was observed at the highest dosage level and the number of live pups per pregnant female on Day 1 postpartum in all dosage groups were comparable to the control group. The incidence of incompletely ossified sternebra was slightly increased in the 320/320 mg/kg/day group compared to the controls. Although these effects are subtle in nature and small in magnitude, they suggest a slight embryotoxic effect of imipenem/cilastatin sodium at high dosage levels in the rat.
TABLE 17 PRINCIPAL REPRODUCTIVE TOXICITY STUDIES WITH IMIPENEM AND CILASTATIN SODIUM FOR INJECTION1
| Type of study | Species, Number/ Sex/Group | Dosage Levels (mg/kg/day) | Principal Effects Observed |
|---|---|---|---|
| Studies with Imipenem Alone | |||
| Teratology, I.V. | Rat, 23 | 100, 300, 900 | No evidence of fetal malformations; no effect postnatal growth and behavior |
| Teratology, I.V. | Rabbit, 20 | 10 , 30 , 60 | No teratogenic effect. |
| Studies with Cilastatin Sodium Alone | |||
| Teratology, I.V., S.C | Rat, 25 | 40, 200 ,1000 | No teratogenic effect. |
| Teratology, I.V., S.C | Rabbit, 10 | 30, 100 , 300 | No teratogenic effect. |
| Studies with Imipenem and Cilastatin Sodium in Combination (Imipenem and cilastatin sodium for injection) | |||
| Fertility, IV/S.C (w/o post- weanling exam) | Rat: 15 male, 30 female | 20/20, 80/80, 320/320 | No evidence of adverse effect on fertility (slight decrease in live fetal weight at 320/320). |
| Teratology, IV | Mouse, 25 | 20/20, 80/80 320/320 | No teratogenic effect |
| Teratology, IV/S.C (with post-natal exam) | Rat, 35 | 20/20, 80/80 320/320 | No teratogenic effect, no adverse effect postnatal growth or behavior. |
| Late Gestation and Lactation IV/S.C | Rat, 20 | 20/20, 80/80 320/320 | No adverse effects observed. |
| Teratology, IV/S.C | Cyanomolgus Monkey, 11 (I.V.), 14 (S.C.) | I.V.: 40/40 , S.C.: 160/160 | Emesis, body weight loss, deaths, abortions at both dose levels; histologic examination of tissues showed no cause of death. No evidence of teratogenicity |
| Teratology by Infusion 45 (total) | Cyanomolgus Monkey | 100/100 ( Days 21-30, 31-40, 41-50) | Drugs infused daily at 3 mg/mL for 10-day periods. No apparent relationship between drug – induced toxicity (emesis) and embryotoxicity. |
1 Although several additional studies were performed to evaluate various aspects of reproduction, the studies presented form the basis of the safety evaluation of imipenem and cilastatin sodium for injection,
Teratology
No evidence of a teratogenic effect was observed in rats or rabbits receiving imipenem or cilastatin sodium alone or in combination. Imipenem alone was evaluated at dosage levels up to 900 mg/kg/day, cilastatin sodium alone at dosage levels up to 1000 mg/kg/day and the two drugs in combination at dosage levels up to 320/320 mg/kg/day in rats.
The characteristic intolerance of rabbits to cephalosporin antibiotics was demonstrated in a teratology study with imipenem alone in this species at a dosage level up to 60 mg/kg/day. Maternotoxicity and feto- and embryotoxicity were observed at 60 mg/kg/day. The embryo- and fetotoxicity is considered to be secondary to the excess maternotoxicity observed in these studies. In the presence of these effects, there was still no evidence of teratogenicity. No evidence of a teratogenic effect was observed in rabbits receiving cilastatin sodium alone at doses up to 300 mg/kg/day.
Monkeys: In a range-finding study imipenem/cilastatin sodium was administered daily by bolus intravenous injection to non-pregnant cynomolgus monkeys for 30 days at doses of 20/20, 60/60, and 120/120 mg/kg/day (4 females per group) in order to establish dosage levels for subsequent studies. Four additional non-pregnant female monkeys were treated with 180/180 mg/kg/day subcutaneously for 30 days and a control group of 4 monkeys were treated intravenously with 0.9% sodium chloride. Emesis or diarrhea were seen on one or two occasions during treatment in some monkeys in the 60/60 and 120/120 mg/kg/day groups. Three animals in the 180/180 mg/kg/day subcutaneous group had occasional diarrhea during treatment.
In a teratology study, a bolus intravenous dose of 40/40 mg/kg/day and a subcutaneous dose of 160/160 mg/kg/day were administered to pregnant cynomolgus monkeys on Days 20 to 50 of gestation (11 and 14 monkeys per group, respectively). A control group of 14 pregnant monkeys were treated with 0.9% sodium chloride I.V. Both doses of imipenem/cilastatin sodium were maternotoxic and resulted in deaths, reduced appetite, body weight loss, diarrhea, and emesis. In the 40/40 and 160/160 mg/kg/day groups, 7 of 11 and 5 of 14 monkeys lost their embryos. This is considered to reflect the obvious maternotoxicity evident at these dosage levels. There was no evidence of a teratogenic effect in surviving fetuses.
A study was conducted to determine the disposition and metabolism of imipenem/cilastatin sodium in pregnant and non-pregnant cynomolgus monkeys (4-5 monkeys per group). A bolus intravenous dose of 100/100 mg/kg/day was administered for 10 days and the first and last dose contained radioactive imipenem. The data suggest that metabolism or disposition is not directly responsible for the increased sensitivity of pregnant monkeys to imipenem/cilastatin sodium-induced toxicity.
In a teratology study in cynomolgus monkeys, imipenem/cilastatin sodium (100/100 mg/kg/day) was administered to 10 pregnant monkeys per group by slow infusion for 3 consecutive 10-day periods (Days 21-30; 31-40; 41-50). Three groups of 5 pregnant monkeys each were similarly treated with the vehicle. Pregnancy was confirmed by tests for macaque chorionic gonadotropin and the maintenance of pregnancy was assessed through periodic ultrasound examinations. Prior to parturition the fetuses were delivered by cesarean section and examined for malformations. Although there was no evidence of fetal external, visceral or skeletal malformations, there was an increase in the incidence of embryonic/fetal loss in the drug-treated monkeys (7 of 30, 23%)
compared to the controls (0 of 15, 0%). Maternotoxicity (emesis and/or gagging during or after treatment) was observed in 4 of the 7 monkeys with embryonic/fetal loss.
Gestation and Postnatal Development
The effect of imipenem/cilastatin sodium during gestation and the postnatal period was studied in rats at doses up to 320/320 mg/kg/day. Imipenem/cilastatin sodium had no effect on growth or survival of offspring.
Genotoxicity
No evidence of drug-induced genetic toxicity was seen in the tests performed with imipenem or cilastatin sodium; these tests are listed in Table 18.
| TABLE 18: PRINCIPAL GENETIC TOXICITY STUDIES WITH IMIPENEM AND CILASTATIN SODIUM FOR INJECTION | |||
|---|---|---|---|
| Type of Study | Species, Number/ Sex/Group | Dosage Levels (mg/kg/day) | Principal Effects Observed |
| Studies with Imipenem Alone | |||
| Mutagenic | V-79 cells | 3, 10, 20 , 36mM final concentration in medium | No evidence of mutagenic activity |
| Studies with Cilastatin Sodium Alone | |||
| Mutagenic | Microbial Mutagenesis (S.typhimurium) | With and without S-9**, 30,100,300, 1000, 2000µg/plate | Negative |
| Studies with Imipenem and Cilastatin Sodium in Combination (Imipenem and cilastatin sodium for injection) | |||
| Mutagenic | V-79 cells | With S-9: 1, 3, 4, 5, 7, 9, 11 mM without S-9: 3, 5, 10, 15 mM | No mutagenic activity detected |
| Mutagenic | Unscheduled DNA synthesis, Rat hepatocytes | 3, 10, 14, 22 mM final concentration in medium | No increase in labelled nuclei |
| Mutagenic | In vivo cytogenetic mouse bone marrow | 59,197,590 mg/kg | No chromosomal aberration seen |
| Mutagenic | In vitro cytogenetic (range-finding) | With and without S-9: 0.2, 0.67, 2.0, 6.7, 20 mM and 2.0, 6.7, 20.0, 67 µm | Increased incidence of sister chromatid exchanges; study repeated and in vitro and in vivo sister chromatid exchange studies performed (below). |
| Mutagenic | In vitro chromosomal aberration assay | With S-9: 8.5, 6.4, 4.2, 2.1, 1.1 mM; without S-9: 21.2, 1.2, 17.0, 12.7, 8.5, 4.2 mM | Negative |
| ** Rat liver microsomal activation system | |||
REFERENCES
- 1. PRIMAXIN® Product Monograph (Merck Canada Inc.). Date of Revision: December 20, 2017. Submission Control No: 204987.