


Product Monograph - Infanrix Hexa
RECENT MAJOR LABEL CHANGES
| Section | Date |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Guillain-Barré Syndrome | SEP 2022 |
| 4 DOSAGE AND ADMINISTRATION, 4.4 Administration | APR 2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 5
4.3 Reconstitution ........................................................................................................ 7
4.4 Administration ........................................................................................................ 8
4.5 Missed Dose ........................................................................................................... 8
5 OVERDOSAGE .............................................................................................................. 8
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 8
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
7.1 Special Populations............................................................................................... 12
7.1.1 Pregnant Women ........................................................................................... 12
7.1.2 Breast-feeding ................................................................................................ 12
7.1.3 Pediatrics ........................................................................................................ 13
8 ADVERSE REACTIONS ................................................................................................ 13
8.1 Adverse Reaction Overview .................................................................................. 13
8.2 Clinical Trial Adverse Reactions ............................................................................ 13
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ................................................... 13
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 15
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics ............................ 15
8.5 Post-Market Adverse Reactions ........................................................................... 15
9 DRUG INTERACTIONS ................................................................................................ 17
9.4 Drug-Drug Interactions ......................................................................................... 17
9.5 Drug-Food Interactions ......................................................................................... 17
9.6 Drug-Herb Interactions ......................................................................................... 17
9.7 Drug-Laboratory Test Interactions ........................................................................ 17
10 CLINICAL PHARMACOLOGY ....................................................................................... 18
10.1 Mechanism of Action ...................................................................................... 18
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 21
PART II: SCIENTIFIC INFORMATION ....................................................................................... 22
13 PHARMACEUTICAL INFORMATION ............................................................................ 22
14 CLINICAL TRIALS ........................................................................................................ 22
14.1 Clinical Trials by Indication ............................................................................. 22
Primary and Booster Vaccination against diphtheria, tetanus, pertussis, hepatitis B, poliomyelitis, and disease caused by Haemophilis influenzae type b ............................. 22
PATIENT MEDICATION INFORMATION .................................................................................. 29
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
1.1 Pediatrics
Primary Immunization
INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) is indicated for:
- active primary immunization against diphtheria, tetanus, pertussis, hepatitis B, poliomyelitis, and disease caused by Haemophilis influenzae type b in infants and children 6 weeks to 2 years.
INFANRIX hexa will not prevent hepatitis caused by other agents, such as hepatitis A, C and E viruses, or other pathogens known to infect the liver. As hepatitis D (caused by the delta virus) does not occur in the absence of hepatitis B infection, it can be expected that hepatitis D will also be prevented by INFANRIX hexa vaccination.
Where a dose of hepatitis B vaccine is given at birth, INFANRIX hexa can be used for the second dose from the age of six weeks. If a second dose of hepatitis B vaccine is required before this age, monovalent Hepatitis B vaccine should be used.
Booster Vaccination
The administration of the booster dose should be given at 12 to 23 months as stated in the Canadian Immunization Guide.
INFANRIX hexa can be used for the booster dose provided that the infant has received a full primary vaccination course of each of the antigens contained in INFANRIX hexa, regardless of whether these were administered as monovalent or combination vaccines.
Other combinations of antigens have been studied in clinical trials following primary vaccination with INFANRIX hexa and may be used for a booster dose, these include diphtheria, tetanus, acellular pertussis (DTaP) and DTaP-Hib.
2 CONTRAINDICATIONS
INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine):
- should not be administered to individuals with known hypersensitivity to any component of this vaccine (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING) or to individuals having shown signs of hypersensitivity after a previous dose of this vaccine or any injection containing diphtheria, tetanus, pertussis, hepatitis B, poliovirus or Haemophilus influenzae type b (see 7 WARNINGS AND PRECAUTIONS, General for information on treatment of immediate allergic reactions).
- should be used with caution in individuals with known hypersensitivity to the antibiotics neomycin and polymyxin, as INFANRIX hexa contains traces of these antibiotics.
- is contraindicated for use after an immediate anaphylactic reaction temporally associated with a previous dose of this vaccine or any injection containing diphtheria, tetanus, pertussis, hepatitis B, poliovirus, or Haemophilus influenzae type b. Because of the uncertainty as to which component of the vaccine might be responsible, no further vaccination with any of these components should be given. Alternatively, because of the importance of tetanus vaccination, such individuals may be referred to an allergist for evaluation.
- should not be administered to persons 7 years of age or older because diphtheria toxoid may cause severe but transient local and febrile reactions in children and adults, the frequency increasing with age, the dose of toxoid and the number of doses given.
- is contraindicated if the infant has experienced an encephalopathy of unknown etiology, occurring within 7 days following previous vaccination with a pertussis containing vaccine. In these circumstances, pertussis vaccination should be discontinued and the vaccination should be continued with diphtheria, tetanus, Hepatitis B, polio, and Hib vaccines.
Immunization should be deferred during the course of a moderate or severe acute febrile illness or acute infection (see 7 WARNINGS AND PRECAUTIONS). The presence of a minor infection, however is not a contraindication.
Elective immunization of individuals over 6 months should be deferred during an outbreak of poliomyelitis.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
The use of reduced volume (fractional doses) is not recommended. The effect of such practices on the frequency of serious adverse events and on protection against disease has not been determined.
Pre-term infants (born after at least 24 weeks of gestational age) should be vaccinated according to their chronological age from birth.
4.2 Recommended Dose and Dosage Adjustment
Primary Immunization
The primary immunization course for infants born of HBsAg-negative mothers is 2 or 3 doses of INFANRIX hexa 0.5 mL, given intramuscularly, which should be administered according to official recommendations (See 14 CLINICAL TRIALS for schedules evaluated in clinical trials). INFANRIX hexa can be considered for the booster if the antigen composition is in accordance with the official recommendations. INFANRIX hexa should not be administered to any infant before the age of 6 weeks.
| Primary vaccination | Booster vaccination | General considerations |
|---|---|---|
| Full-term infants (> 6 weeks of age) | ||
| 3-dose | A booster dose must be given. |
|
| 2-dose | A booster dose must be given. |
|
| Preterm infants born after at least 24 weeks of gestational age (> 6 weeks of age) | ||
| 3-dose | A booster dose must be given. |
|
Children Previously Vaccinated with One or More Doses of Hepatitis B Vaccine
Children who receive one dose of Hepatitis B vaccine at or shortly after birth may be administered a 3-dose series of INFANRIX hexa vaccine starting as early as 6 weeks of age. There is no data to support the use of a 3-dose series of INFANRIX hexa in infants who have previously received more than one dose of Hepatitis B vaccine. INFANRIX hexa may be administered to infants otherwise scheduled to receive concurrent INFANRIX (diphtheria, tetanus and acellular pertussis vaccine) and Hepatitis B vaccine and in whom vaccination against poliovirus is also desired.
Additional Dosing Information
If any recommended dose of pertussis vaccine cannot be given, diphtheria and tetanus toxoids (DT) for pediatric use should be given as needed to complete the series.
For persons 7 years of age or older, Tetanus and Diphtheria Toxoids (Td) for adult use should be given for routine booster immunization against tetanus and diphtheria.
4.3 Reconstitution
INFANRIX hexa (Combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) should not be mixed with any other vaccine in the same syringe or vial.
Upon storage, a white deposit and clear supernatant may be observed in the syringe. This is a normal observation and does not constitute a sign of deterioration. Shake the syringe well before use. With thorough agitation, DTaP-HB-IPV (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant) and inactivated poliomyelitis vaccine, tradename PEDIARIX) is a homogeneous white turbid suspension. The syringe and the vial containing the Hib powder should be inspected visually for any foreign particulate matter and/or variation of physical aspect. In the event of either being observed, do not administer the vaccine, and any unused vaccine or waste material should be disposed of in accordance with local requirements. The vaccine is reconstituted by adding the entire contents of the syringe (PEDIARIX) to the vial containing the Hib powder. After the addition of the PEDIARIX vaccine to the powder, the mixture should be well shaken until the powder is completely dissolved. The vaccine should not be mixed with other vaccines.
It is good clinical practice to only inject a vaccine when it has reached room temperature. In addition, a vial at room temperature ensures sufficient elasticity of the rubber closure to minimise any coring of rubber particles. To achieve this, the vial should be kept at room temperature (25 ± 3 °C) for at least five minutes before connecting the syringe and reconstituting the vaccine.
The reconstituted vaccine presents as a slightly more cloudy suspension than the liquid component alone. This is a normal observation. The reconstituted vaccine should be inspected visually for any foreign particulate matter and/or abnormal physical appearance. In the event of either being observed, do not administer the vaccine, and any unused vaccine or waste material should be disposed of in accordance with local requirements.
Since this product is a suspension containing an adjuvant, shake vigorously to obtain a uniform suspension prior to withdrawal from the vial. Do not use if resuspension does not occur with vigorous shaking. Withdraw the entire contents of the vial.
INFANRIX hexa should be administered by intramuscular injection. The preferred sites are the anterolateral aspects of the thigh or the deltoid muscle of the upper arm. The vaccine should not be injected in the gluteal area or areas where there may be a major nerve trunk. Before injection, the skin at the injection site should be cleaned and prepared with a suitable germicide. After insertion of the needle, aspirate to ensure that the needle has not entered a blood vessel.
Do not administer this product subcutaneously or intravenously.
After reconstitution, the vaccine should be injected promptly. However the vaccine may be kept for up to 8 hours at room temperature (21°C).
4.4 Administration
Preparation for Administration
The vaccine is reconstituted by adding the entire contents of the syringe (PEDIARIX) to the vial containing the Hib powder.
Pre-filled syringe Instructions
Hold the syringe by the barrel, not by the plunger. Unscrew the syringe cap by twisting it anticlockwise. | |
|---|---|
To attach the needle, connect the hub to the Luer Lock Adaptor and rotate a quarter turn clockwise until you feel it lock. Do not pull the syringe plunger out of the barrel. If it happens, do not administer the vaccine. |
4.5 Missed Dose
Interruption of the recommended schedule with a delay between doses should not interfere with the final immunity achieved with INFANRIX hexa. There is no need to start the series over again regardless of the time elapsed between doses.
5 OVERDOSAGE
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
To help ensure the traceability of biologic products, including biosimilars, health professionals should recognise the importance of recording both the brand name and the non-proprietary (active ingredient) name as well as other product-specific identifiers such as the Drug Identification Number
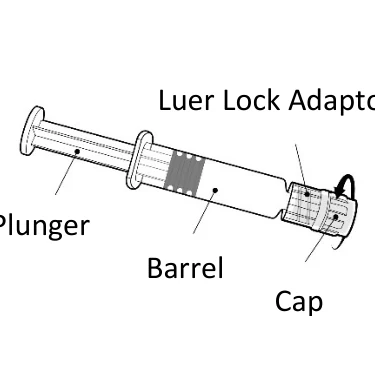 Plunger Barrel Cap Luer Lock Adaptor | |
|---|---|
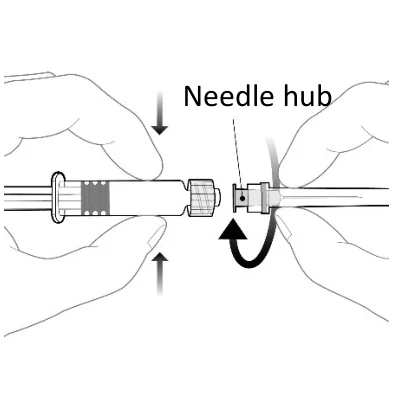 Needle hub |
(DIN) and the batch/lot number of the product supplied.
Table 1 – Administration Route, Dosage Form, Strength, Nonmedical Ingredients
| Route of Administration | Dosage Form/Strength | Nonmedicinal Ingredients |
| Intramuscular injection | Suspension for injection/ After reconstitution, 1 dose (0.5 mL) contains 25 limit of flocculation (Lf) [30 International Units (IU)] diphtheria toxoid; 25 mcg filamentous haemagglutinin (FHA); 10 mcg hepatitis B surface antigen (HBsAg); 8 mcg pertactin (PRN); 25 mcg pertussis toxoid (PT); 40 D-antigen units (DU) of type 1 poliovirus, 8 DU type 2 poliovirus, and 32 DU type 3 poliovirus ; 10 Lf (40 IU) tetanus toxoid; 10 mcg of adsorbed purified capsular polysaccharide of Haemophilus influenzae type b (Hib) (PRP) covalently bound to approximately 25 mcg of tetanus toxoid per 0.5 mL dose. | 0.82 mg aluminum (as aluminum salts), 12.6 mg lactose, 1.15 mg medium 199, 4.5 mg sodium chloride, water for injection. Residues*: neomycin sulphate and polymyxin B sulphate. |
*From the manufacturing process.
Packaging
Syringe and Vial
PEDIARIX (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant) and inactivated poliomyelitis vaccine) is supplied as a turbid suspension in a pre-filled syringe (Type I glass) (0.5 mL) with a plunger stoppers (butyl rubber).
Haemophilus influenzae type b vaccine is supplied as powder in a 3.0 mL vial (Type I glass) with stopper (butyl rubber).
Supplied as a kit in pack sizes of 10 with or without needles.
Description
INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) contains diphtheria toxoid, tetanus toxoid, three purified pertussis antigens [pertussis toxoid (PT), filamentous haemagglutinin (FHA) and pertactin (PRN) (69 kiloDalton outer membrane protein)], hepatitis B virus surface antigen recombinant, adsorbed onto aluminum salts, purified, inactivated poliovirus types 1, 2 and 3, Haemophilus influenzae type b polysaccharide conjugated to tetanus toxoid.
7 WARNINGS AND PRECAUTIONS
General
Do not administer INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) intravascularly or intradermally.
As with any other vaccine, a protective immune response may not be elicited in all vaccinees for all component antigens in the vaccine. This product is not recommended for treatment of actual infections.
INFANRIX hexa will not prevent disease caused by pathogens other than Corynebacterium diphtheria, Clostridium tetani, Bordetella pertussis, hepatitis B virus, poliovirus or Haemophilus influenzae type b.
As for all diphtheria, tetanus and pertussis vaccines, each injection should be given deep intramuscularly and each injection of the immunization series should be made at a different site.
As with other injectable vaccines, epinephrine injection (1:1000) and other appropriate agents used for the control of immediate allergic reactions must be immediately available should an acute anaphylactic reaction occur. For this reason, the vaccinee should remain under medical supervision for 30 minutes after immunization.
It is good clinical practice that vaccination should be preceded by a review of the medical history (especially with regard to previous vaccination and possible occurrence of undesirable events) and a clinical examination.
Where passive protection is required, Tetanus Immune Globulin and/or Diphtheria Antitoxin may also be administered at separate sites. Because of the substantial risks of complications from pertussis disease, completion of a primary series of vaccine early in life is strongly recommended.
If any of the following events occur in temporal relation to administration of whole-cell DTP or acellular DTP vaccine, the decision to give subsequent doses of vaccine containing the pertussis component should be carefully considered:
- Temperature of > 40.5º C within 48 hours of vaccination not due to another identifiable cause.
- Collapse or shock-like state (hypotonic hyporesponsive episode) within 48 hours of vaccination.
- Persistent, inconsolable crying lasting ≥ 3 hours, occurring within 48 hours of vaccination.
- Convulsions with or without fever occurring within 3 days of vaccination.
There may be circumstances, such as high incidence of pertussis, in which the potential benefits outweigh possible risks, particularly since these events have not been proven to cause permanent sequelae.
Data from clinical studies indicate that, when INFANRIX hexa is co-administered with pneumococcal conjugate vaccine (PREVNAR*, PREVNAR* 13 or SYNFLORIX), the rate of febrile reactions is higher compared to that occurring following the administration of INFANRIX hexa alone.
Increased reporting rates of convulsions (with or without fever) and hypotonic hyporesponsive episode were observed with concomitant administration of INFANRIX hexa and PREVNAR* 13 (see 8 ADVERSE REACTIONS).
Antipyretic treatment should be initiated according to local treatment guidelines.
Syncope (fainting) can occur following, or even before, any vaccination as a psychogenic response to the needle injection. It is important that procedures are in place to avoid injury from faints.
*Trademark owned by Wyeth LLC
Guillain-Barré Syndrome
A review by the National Academy of Medicine found evidence for a causal relationship between receipt of tetanus toxoid and both Guillain-Barré syndrome (GBS) and brachial neuritis. If GBS occurred within 6 weeks of receipt of prior vaccine containing tetanus toxoid, the decision to give INFANRIX hexa or any vaccine containing tetanus toxoid should be based on careful consideration of the potential benefits and possible risks.
Hematologic
INFANRIX hexa should be administered with caution to individuals with thrombocytopenia or a bleeding disorder since bleeding may occur following intramuscular administration to these individuals.
Hepatitis B
Infants born of HBsAg-positive mothers should receive hepatitis B immune globulin (HBIG) and Hepatitis B vaccine at birth and should complete the Hepatitis B vaccination series given according to a particular schedule. Infants born of mothers of unknown HBsAg status should receive Hepatitis B vaccine at birth and should complete the Hepatitis B vaccination series given according to a particular schedule (see Manufacturer's package insert for Hepatitis B vaccine).
The subsequent administration of INFANRIX hexa for completion of the Hepatitis B vaccination series in infants who were born of HBsAg-positive mothers and received HBIG, or infants born of mothers of unknown status has not been studied.
Immune
Hepatitis B has a long incubation period. Hepatitis B vaccination may not prevent hepatitis B infection in individuals who had an unrecognized hepatitis B infection at the time of vaccine administration.
INFANRIX hexa is not contraindicated for use in individuals with HIV infection. The expected immunological response may not be obtained after vaccination of immunosuppressed individuals.
Immunosuppressive therapies, including irradiation, antimetabolites, alkylating agents, cytotoxic drugs and corticosteroids (used in greater than physiologic doses), may reduce the immune response to vaccines (See 9 DRUG INTERACTIONS).
Monitoring and Laboratory Tests
Interference with laboratory testing
The Hib component of the vaccine does not protect against diseases due to capsular serotypes other than type b of Haemophilus influenzae or against meningitis caused by other organisms. Excretion of capsular polysaccharide antigen in the urine has been described following administration of Hib vaccines, and therefore antigen detection may not have a diagnostic value in suspected Hib disease within 1-2 weeks of vaccination. Other tests should be performed in order to confirm Hib infection during this period.
Neurologic
Experience with INFANRIX (DTaP) and other INFANRIX-based combinations has not revealed any cases of encephalopathy or permanent neurologic damage causally linked to vaccination. While acute encephalopathy and permanent neurologic damage have not been reported to be causally linked nor in a temporal association with administration of INFANRIX hexa data is limited at this time.
In children with progressive neurological disorders, including infantile spasms, uncontrolled epilepsy or progressive encephalopathy, it is better to defer pertussis (Pa or Pw) immunization until the condition is corrected or stable. However, the decision to give pertussis vaccine must be made on an individual basis after careful consideration of the risks and benefits.
A history of convulsions or other central nervous system disorders in parents or siblings is not a contraindication for INFANRIX hexa, an acellular DTP vaccine. Vaccinees with a history of febrile convulsions should be closely followed up as such adverse events may occur within 2 to 3 days post vaccination.
Studies suggest that when given whole-cell DTP vaccine, infants and children with a history of convulsions in first-degree family members (i.e., siblings and parents) have a 2.4-fold increased risk for neurologic events compared to those without such histories.
Respiratory
Although a moderate or severe illness with or without fever is a reason to defer vaccination, minor illnesses such as mild upper respiratory infections with or without low-grade fever are not a contraindication.
7.1 Special Populations
7.1.1 Pregnant Women
As INFANRIX hexa is not intended for use in adults, adequate human data on use during pregnancy and adequate animal reproduction studies are not available.
7.1.2 Breast-feeding
As INFANRIX hexa is not intended for use in adults, adequate human data on use during lactation and adequate animal reproduction studies are not available.
7.1.3 Pediatrics
Clinical data indicate that INFANRIX hexa can be given to preterm infants, however, as expected in this population, a lower immune response has been observed for some antigens (see 8 ADVERSE REACTIONS and 14 CLINICAL TRIALS). The potential risk of apnea and the need for respiratory monitoring for 48-72h should be considered when administering the primary immunization series to very preterm infants (born after at least 24 weeks of gestational age) and particularly for those with a previous history of respiratory immaturity. As the benefit of vaccination is high in these infants, vaccination should not be withheld or delayed. Safety and effectiveness of INFANRIX hexa have not been established in infants below the age of 6 weeks and children over 2 years of age.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) is generally well tolerated.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
During a study conducted in the United States, a total of 785 documented doses of study vaccines were given to 267 subjects included in the According To Protocol (ATP) reactogenicity analysis. Solicited and unsolicited symptoms occurring during the 8-day follow-up period after vaccination were reported. Most reported solicited local symptoms and solicited general symptoms were mild to moderate in intensity. There were no statistically significant differences between the two groups in the incidence of soreness, redness or swelling at the injection site (regardless of side/site/dose) or fever. The percentage of subjects per group experiencing symptoms (both solicited and unsolicited) during the 8 days after vaccination is outlined in Table 2.
Table 2 - Percentage of U.S. Infants with Local or Systemic Reactions within 8 Days of Primary Vaccination with either INFANRIX hexa or Commercially Available INFANRIX, ENGERIX-B, and OPV Administered Simultaneously with Hib at Separate Sites (Per subject analysis)
| Event | INFANRIX hexa (N=134) | INFANRIX, ENGERIX–B, Hib vaccine, OPV (N=133) |
|---|---|---|
| Local | % | % |
| Pain, any | 42.54 | 52.63 |
| Pain, severe | 1.49 | 2.26 |
| Redness, any | 48.51 | 47.37 |
| Redness, > 20 mm | 2.24 | 3.01 |
|---|---|---|
| Swelling, any | 35.82 | 40.60 |
| Swelling, > 20 mm | 3.73 | 4.51 |
| Systemic | % | % |
| Temperature | ||
| ≥ 38°C | 55.97 | 51.88 |
| > 39.5°C | 0.75 | 2.26 |
| Diarrhea, any | 35.82 | 33.08 |
| Grade 3 | 0.75 | 2.26 |
| Eating/drinking less than usual, any | 49.25 | 57.14 |
| Grade 3 | 2.24 | 2.26 |
| Irritability/fussiness, any | 82.84 | 86.47 |
| Grade 3 | 6.72 | 6.02 |
| Sleeping less than usual, any | 50.75 | 56.39 |
| Grade 3 | 2.24 | 3.76 |
| Sleeping more than usual, any | 62.69 | 67.67 |
| Grade 3 | 3.73 | 1.50 |
| Unusual crying for more than one hour, any | 42.54 | 41.35 |
| Grade 3 | 3.73 | 2.26 |
| Vomiting, any | 25.37 | 20.30 |
| Grade 3 | 0.75 | 0.75 |
N= number of infants
The safety profile presented below is based on data from more than 16,000 subjects.
As has been observed for DTaP and DTaP-containing combinations, an increase in local reactogenicity and fever was reported after booster vaccination with INFANRIX hexa with respect to the primary course.
Frequencies per dose as defined by CIOMS:
Very common: ≥ 10%
Appetite lost, irritability, crying abnormal, restlessness, pain, redness, local swelling at the injection site (≤ 50 mm), fever ≥ 38°C, and somnolence.
Common: ≥ 1% and < 10%
Nervousness, vomiting, diarrhea, local swelling at the injection site (> 50 mm)*, fever >39.5°C, pruritis** and injection site reactions, including induration.
* Children primed with acellular pertussis vaccines are more likely to experience swelling reactions after booster administration in comparison with children primed with whole cell vaccines. These reactions resolve over an average of 4 days.
**Observed only with other GSK DTaP-containing vaccines.
Local reactions after immunization usually consist of swelling or induration, tenderness, and redness or erythema at the injection site. More severe local reactions occasionally occur, such as inflammatory cellulitis without bacterial infection after DTP-containing vaccines.
8.3 Less Common Clinical Trial Adverse Reactions
8.3.1 Less Common Clinical Trial Adverse Reactions – Pediatrics
The safety profile presented below is based on data from more than 16,000 subjects.
Frequencies per dose as defined by CIOMS:
Uncommon: ≥ 0.1% and < 1%
Upper respiratory tract infection, fatigue, cough** and diffuse swelling of the injected limb, sometimes involving the adjacent joint*.
Rare: ≥ 0.01% and < 0.1%
Bronchitis and rash.
Very rare: < 0.01%
Convulsions (with or without fever)***, dermatitis, bronchospasm, and urticaria**.
* Children primed with acellular pertussis vaccines are more likely to experience swelling reactions after booster administration in comparison with children primed with whole cell vaccines. These reactions resolve over an average of 4 days.
**Observed only with other GSK DTaP-containing vaccines.
*** Analysis of post-marketing reporting rates suggests a potential increased risk of convulsions (with or without fever) and hypotonic hyporesponsive episode when comparing groups which reported use of INFANRIX hexa with PREVNAR* 13 to those which reported use of INFANRIX hexa alone.
*Trademark owned by Wyeth LLC
8.5 Post-Market Adverse Reactions
Over 12 million doses of INFANRIX hexa have been distributed overall for primary and booster vaccinations. Extremely rare cases of Sudden Unexpected Death (SUD) in close temporal association to vaccination with INFANRIX hexa have been reported in the first year of life. However, a causal relationship has not been established. The observed number of SUD cases following INFANRIX hexa is below the number of cases expected to occur by chance.
Blood and lymphatic system disorders
Lymphadenopathy, thrombocytopenia.
Immune system disorders
Allergic reactions (including anaphylactic and anaphylactoid reactions).
Nervous system disorders
Collapse or shock-like state (hypotonic hyporesponsive episode)***.
Respiratory, thoracic and mediastinal disorders
Apnea** [see 7 WARNINGS AND PRECAUTIONS for apnea in very premature infants (≤ 28 weeks of gestation)].
Skin and subcutaneous tissue disorders
Angioneurotic oedema**.
General disorders and administration site conditions
Extensive swelling reactions, swelling of the entire injected limb*, vesicles at the injection site.
*Children primed with acellular pertussis vaccines are more likely to experience swelling reactions after booster administration in comparison with children primed with whole cell vaccines. These reactions resolve over an average of 4 days.
**Observed only with other GSK DTaP-containing vaccines.
*** Analysis of post-marketing reporting rates suggests a potential increased risk of convulsions (with or without fever) and hypotonic hyporesponsive episode when comparing groups which reported use of INFANRIX hexa with PREVNAR* 13 to those which reported use of INFANRIX hexa alone.
* Trademark owned by Wyeth LLC
Safety in preterm infants
INFANRIX hexa has been administered to more than 1,000 preterm infants (born after a gestation period of 24 to 36 weeks) in primary vaccination studies and in more than 200 preterm infants as a booster dose in the second year of life. In comparative studies, similar rates of symptoms were observed in preterm and full-term infants.
Safety in infants and toddlers born to mothers vaccinated with Tdap (BOOSTRIX) during pregnancy
In clinical studies, INFANRIX hexa has been administered to more than 500 subjects born to mothers vaccinated with Tdap (BOOSTRIX) or placebo after 27 weeks of pregnancy. The safety profile of INFANRIX hexa was similar regardless of exposure/non-exposure to Tdap during pregnancy.
Experience with hepatitis B vaccine
Paralysis, neuropathy, Guillain-Barré syndrome, encephalopathy, encephalitis, meningitis, allergic reactions mimicking serum sickness, neuritis, hypotension, vasculitis, lichen planus, erythema multiforme, arthritis and muscular weakness have been reported extremely rarely during post-marketing surveillance following vaccination with ENGERIX-B (Hepatitis B vaccine) in infants and children < 2 years old. The causal relationship to the vaccine has not been established.
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
The drugs listed below are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Interactions with other drugs have not been established.
Anticoagulants
As with other intramuscular injections, INFANRIX hexa should not be given to infants or children on anticoagulant therapy unless the potential benefit clearly outweighs the risk of administration (see 7 WARNINGS AND PRECAUTIONS).
Immunosuppressive Therapies
Immunosuppressive therapies, including irradiation, antimetabolites, alkylating agents, cytotoxic drugs and corticosteroids (used in greater than physiologic doses), may reduce the immune response to vaccines. Although no specific data are available from studies with INFANRIX hexa under these conditions, if immunosuppressive therapy will be discontinued shortly, it would be reasonable to defer immunization until the individual has been off therapy for 3 months; otherwise, the individual should be vaccinated while still on therapy. If INFANRIX hexa is administered to a person receiving immunosuppressive therapy, or a recent injection of immune globulin, an adequate immunologic response may not be obtained.
Use with Other Vaccines
Tetanus Immune Globulin or Diphtheria Antitoxin, if used, should be given at a separate site, with a separate needle and syringe.
INFANRIX hexa can be given concomitantly with pneumococcal conjugate, MenC conjugate, MenACWY conjugate, rotavirus, measles, mumps, rubella and varicella vaccines. Data have shown no clinically relevant interference in the antibody response to each of the individual antigens in INFANRIX hexa.
Data from clinical studies indicate that, when INFANRIX hexa is co-administered with pneumococcal conjugate vaccine, the rate of febrile reactions is higher compared to that occurring following the administration of INFANRIX hexa (see 7 WARNINGS AND PRECAUTIONS, General). The incidence of fever following administration of the two vaccines in the primary series was lower than that observed after the booster vaccination.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Diphtheria
Diphtheria is a serious communicable disease, primarily a localized and generalized intoxication caused by diphtheria toxin, an extracellular protein metabolite of toxigenic strains of Corynebacterium diphtheriae. The disease occurs most frequently in unimmunized or partially immunized individuals. The incidence of diphtheria in Canada has decreased from 9,000 cases reported in 1924 to extremely low levels. Only 1 or 2 cases have been reported annually in recent years. The case fatality rate remains 5% to 10 %, with the highest death rates in the very young and elderly. If immunization levels are allowed to fall and adults do not receive booster doses, disease re-emergence may appear as demonstrated in the Commonwealth of Independent States (former Soviet Union), where tens of thousands of cases with substantial mortality have been reported. Protection against disease is due to the development of neutralizing antibodies to the diphtheria toxin. Following adequate immunization with diphtheria toxoid, it is thought that protection persists for at least 10 years. Serum antitoxin levels of at least 0.01 antitoxin units per mL are generally regarded as protective.
This significantly reduces both the risk of developing diphtheria and the severity of clinical illness. Immunization with diphtheria toxoid does not, however, eliminate carriage of C. diphtheriae in the pharynx, nose or on the skin.
Tetanus
Tetanus is an intoxication manifested primarily by neuromuscular dysfunction caused by a potent exotoxin released by Clostridium tetani. Immunization is highly effective, provides long-lasting protection and is recommended for the whole population. Only 1 to 7 with an average of 5 cases of tetanus are now reported annually in Canada, while no deaths have been recorded since 1995. The disease continues to occur almost exclusively among persons who are unvaccinated, inadequately vaccinated or whose vaccination histories are unknown or uncertain.
Spores of C. tetani are ubiquitous. Naturally acquired immunity to tetanus toxin does not occur. Thus, universal primary immunization and timed booster doses to maintain adequate tetanus antitoxin levels are necessary to protect all age groups. Protection against disease is due to the development of neutralizing antibodies to the tetanus toxin. Tetanus toxoid is a highly effective antigen and a completed primary series generally induces serum antitoxin levels of at least 0.01 antitoxin units per mL, a level which has been reported to be protective. It is thought that protection persists for at least 10 years.
Pertussis
Pertussis (whooping cough) is a disease of the respiratory tract caused by Bordetella pertussis. Pertussis is highly communicable and can affect individuals of any age; however, severity is greatest among young infants.
A study was conducted in Germany to assess the efficacy of pertussis vaccine after partial and completed primary vaccination series for preventing hospitalizations due to pertussis under field conditions. Data was acquired by a nationwide, hospital based, active surveillance system. After one dose of the vaccine, vaccine effectiveness was as high as 68%, increasing to 91.8% after receipt of the second dose. Vaccine effectiveness of 3 and 4 doses of acellular vaccine were estimated to be 99.8% and 98.6%, respectively.
Antigenic components of B. pertussis believed to contribute to protective immunity include: pertussis toxin (PT); filamentous hemagglutinin (FHA); and pertactin. Although the role of these antigens in providing protective immunity in humans is not well understood, clinical trials which evaluated candidate acellular DTP vaccines manufactured by GlaxoSmithKline supported the efficacy of 3 component INFANRIX (DTaP). Recently published data suggests a higher importance of the PT and pertactin components in providing protection against pertussis.
INFANRIX contains 3 pertussis antigens (PT, FHA and pertactin), and has been shown to be effective in preventing World Health Organization (WHO)-defined pertussis as well as clinically milder disease in two published clinical trials when administered as a primary series.
A double-blind, randomized, placebo (DT)-controlled trial conducted in Italy, sponsored by the U.S. National Institutes of Health (NIH), assessed the absolute protective efficacy of INFANRIX when administered at 2, 4 and 6 months of age. A total of 15,601 infants were immunized with 1 of 2 tri-component acellular DTP vaccines (containing inactivated PT, FHA and pertactin), or with a whole-cell DTP vaccine manufactured by Sanofi Pasteur, or with DT vaccine alone. The mean length of follow-up was 17 months, beginning 30 days after the third dose of vaccine. The population used in the primary analysis of vaccine efficacy included 4,481 INFANRIX vaccinees, 4,348 whole-cell DTP vaccinees and 1,470 DT vaccinees. After 3 doses, the protective efficacy of INFANRIX against WHO-defined typical pertussis (21 days or more of paroxysmal cough with infection confirmed by culture and/or serologic testing) was 84% (95% CI: 76% to 89%) while the efficacy of the whole-cell DTP vaccine was 36% (95% CI: 14% to 52%). When the definition of pertussis was expanded to include clinically milder disease with respect to type and duration of cough, with infection confirmed by culture and/or serologic testing, the efficacy of INFANRIX was calculated to be 71% (95% CI: 60% to 78%) against > 7 days of any cough and 73% (95% CI: 63% to 80%) against ≥14 days of any cough. A longer follow-up of the Italian trial showed that after 3 doses, the absolute efficacy of INFANRIX against WHO-defined pertussis remained high at 84% among children up to 4 years of age.
A prospective, blinded efficacy trial was also conducted in Germany employing a household contact study design. In preparation for this study, 3 doses of INFANRIX were administered at 3, 4 and 5 months of age to more than 22,000 children living in 6 areas of Germany in a large safety and immunogenicity trial. Infants who did not participate in this trial could have received whole-cell DTP vaccine (manufactured by Chiron Behring, Germany) or DT vaccine. Calculation of vaccine efficacy was based on attack rates of pertussis in household contacts classified by vaccination status. Of the 173 unvaccinated household contacts, 96 developed WHO-defined pertussis (21 days or more of paroxysmal cough with infection confirmed by culture and/or serologic testing), as compared to 7 of 112 contacts vaccinated with INFANRIX and 1 of 75 contacts vaccinated with whole-cell DTP vaccine. The protective efficacy of INFANRIX was calculated to be 89% (95% CI: 77% to 95%), with no indication of waning of immunity up until the time of the booster. The protective efficacy of the whole-cell DTP vaccine was calculated to be 98% (95% CI: 83% to 100%). When the definition of pertussis was expanded to include clinically milder disease, with infection confirmed by culture and/or serologic testing, the efficacy of INFANRIX against ≥7 days of any cough was 67% (95% CI: 52% to 78%) and against ≥7 days of paroxysmal cough was 81% (95% CI: 68% to 89%). The corresponding efficacy rates of INFANRIX against ≥14 days of any cough or paroxysmal cough were 73% (95% CI: 59% to 82%) and 84% (95% CI: 71% to 91%), respectively.
Hepatitis B
Several hepatitis viruses are known to cause a systemic infection resulting in major pathologic changes in the liver (e.g., A, B, C, D, E). Hepatitis B infection can have serious consequences including acute massive hepatic necrosis, chronic active hepatitis and cirrhosis of the liver. It has been estimated that more than 350 million people in the world are persistently infected with hepatitis B virus.
Among infected infants, very few (5 -10%) recover completely; the majority (up to 90%) become chronic carriers with the risk of becoming a chronic carrier decreasing with age (children < 5 years 25% to 50%, adults 6% to 10%). Those individuals who become chronic carriers can infect others and are at increased risk of developing either cirrhosis or primary hepatocellular carcinoma.
Among other factors, infection with hepatitis B may be the single most important factor for development of this carcinoma. Considering the serious consequences of infection, immunization should be considered for all persons.
Mothers infected with hepatitis B virus can infect their infants at, or shortly after, birth if they are carriers of the hepatitis B surface antigen (HBsAg) or develop an active infection during the third trimester of pregnancy. Infected infants usually become chronic carriers. Therefore, screening of pregnant women for hepatitis B is recommended. According to the Canadian Immunization Guide, hepatitis B prevention should include programs for universal immunization of children, pre-exposure vaccination of high-risk groups, universal HBsAg screening of all pregnant women and post-exposure intervention for those exposed to disease, particularly infants born to hepatitis B-infected mothers. There is no specific treatment for acute hepatitis B infection. However, those who develop anti-HBs antibodies after active infection are usually protected against subsequent infection. Antibody titers ≥10 mIU/mL against HBsAg are recognized as conferring protection against hepatitis B. Seroconversion is defined as antibody titers ≥1 mIU/mL.
Poliomyelitis
Poliovirus is an enterovirus that belongs to the picornavirus family. Three serotypes of poliovirus have been identified (types 1, 2 and 3). Poliovirus is highly contagious with the predominant mode of transmission being person-to-person via the fecal-oral route. Infection may be spread indirectly through contact with infectious saliva or feces or by contaminated water or sewage.
Replication of poliovirus in the pharynx and intestine is followed by a viremic phase where involvement of the central nervous system can occur. While poliovirus infections are asymptomatic or cause nonspecific symptoms (low-grade fever, malaise, anorexia and sore throat) in 90% to 95% of individuals, 1% to 2% of infected persons will develop paralytic disease.
Following the introduction of inactivated poliovirus vaccines (IPV) in Canada in 1955, the indigenous disease has been eliminated. Since 1980, 12 paralytic cases have been reported in Canada, 11 of which were determined to be vaccine-associated paralytic poliomyelitis (VAPP), with Oral Polio Vaccine (OPV). The last reported case of VAPP occurred in 1995.
Forty seven studies involving over 19,000 infants and children have been conducted in developed and developing countries with GlaxoSmithKline’s enhanced inactivated poliovirus vaccine, as trivalent IPV vaccine or as a part of DTaP-IPV based combinations.
Haemophilus Influenzae type b
Haemophilus influenzae type b (Hib) was the most common cause of bacterial meningitis and a leading cause of other serious invasive infections in young children prior to the introduction of other Hib vaccines. About 55% to 65% of affected children had meningitis while the remainder had epiglottitis, bacteremia, cellulitis, pneumonia or septic arthritis. The case fatality rate of meningitis is about 5%. Severe neurologic sequelae occur in 10% to 15% of survivors and deafness in 15% to 20% (severe in 3% to 7%).
Before the introduction of Hib conjugate vaccines in Canada in 1988, there were approximately 2,000 cases of Hib disease annually. Since then the overall incidence has fallen by more than 99%. The majority of cases occur now in children too old to have received primary vaccination. In 1998, only 15 cases were reported in children < 5 years of age.
11 STORAGE, STABILITY AND DISPOSAL
Store INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) at 2° to 8°C. Do not use after the expiration date shown on the label. After reconstitution, immediate use is recommended. However, stability of the vaccine has been demonstrated for 8 hours at 21°C after reconstitution.
Do not freeze. Discard if the vaccine has been frozen.
Protect from light.
During transport, recommended conditions of storage must be respected.
Stability data indicate that the vaccine components are stable at temperatures up to 25°C for 72 hours. These data are intended to guide healthcare professionals in case of temporary temperature excursion only.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine
Product Characteristics
INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) contains combined diphtheria and tetanus toxoids, hepatitis B virus surface antigen recombinant, three purified pertussis antigens [pertussis toxoid (PT), filamentous haemagglutinin (FHA), pertactin (69 kiloDalton outer membrane protein)], adsorbed onto aluminum salts, and purified, inactivated poliovirus types 1, 2 and 3, and Haemophilus influenzae type b polysaccharide conjugated to tetanus toxoid.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Primary and Booster Vaccination against diphtheria, tetanus, pertussis, hepatitis B, poliomyelitis, and disease caused by Haemophilis influenzae type b
The immunogenicity of INFANRIX hexa has been evaluated in clinical studies from 6 weeks of age. The vaccine was assessed in 2-dose and 3-dose priming schedules, including the schedule for the Expanded Program on Immunization, and as a booster dose. The results of these clinical studies are summarized below.
Immune Response to INFANRIX hexa Administered as a 3 Dose Primary Series
A total of 14,600 doses of INFANRIX hexa (combined diphtheria and tetanus toxoids, acellular pertussis, hepatitis B (recombinant), inactivated poliomyelitis, and adsorbed conjugated Haemophilus influenzae type b vaccine) have been administered to 4,890 infants from 6 weeks of age and up as a primary series in clinical studies.
The immune responses to each of the antigens contained in INFANRIX hexa were evaluated in sera obtained 1 month after the third dose of vaccine as compared to that following administration of commercially available vaccines (INFANRIX (diphtheria, tetanus, and acellular pertussis vaccine), ENGERIX-B (hepatitis B vaccine (recombinant)), Hib vaccine, and Oral Polio Virus vaccine) simultaneously at separate sites, in a study conducted in the U.S. The schedule of administration was 2, 4, and 6 months of age. One month after the third dose of INFANRIX hexa, immune response rates to each antigen were comparable to rates seen following separately administered vaccines (see Table 3).
The immunogenicity of INFANRIX hexa was evaluated across three studies including approximately 300 preterm infants (born after a gestation period of 24 to 36 weeks) following a 3-dose primary vaccination course at 2, 4 and 6 months of age. The immunogenicity of a booster dose at 18 to 24 months of age was evaluated in approximately 200 preterm infants (see Immunogenicity in preterm infants below).
Table 3 - Antibody Responses to Each Antigen Following INFANRIX hexa as Compared to INFANRIX, ENGERIX-B, Hib vaccine, and OPV (One Month After Administration of Dose 3)
INFANRIX hexa (N=78-106) | INFANRIX, ENGERIX-B, Hib vaccine, OPV (N=71-98) | |
Anti-Diphtheria % ≥ 0.1 IU/mL | 100.0 | 99.0 |
| GMT | 1.431 | 1.009 |
Anti-Tetanus % ≥ 0.1 IU/mL | 100.0 | 100.0 |
| GMT | 1.979 | 1.486 |
Anti-PT (V.R.) % R | 99.0 | 97.9 |
| GMT | 67.4 | 41.8 |
Anti-FHA (V.R.) % R | 100.0 | 98.7 |
| GMT | 288.0 | 302.8 |
Anti-Pertactin (V.R.) % R | 96.2 | 95.8 |
| GMT | 168.2 | 136.9 |
Anti-HBs % ≥ 10 mIU/mL | 99.1 | 100.0 |
| GMT | 1239.5 | 934.3 |
Anti-Polio 1 % ≥ 8 | 100.0 | 98.6 |
| GMT | 494.8 | 1278.2 |
Anti-Polio 2 % ≥ 8 | 98.8 | 100.0 |
| GMT | 507.4 | 1350.4 |
Anti-Polio 3 % ≥ 8 | 98.8 | 98.6 |
| GMT | 1275.1 | 367.5 |
Anti-PRP % ≥ 0.15 mcg/mL | 100.0 | 96.9 |
Anti-PRP % ≥ 1.0 mcg/mL | 84.0 | 91.8 |
| GMT | 2.648 | 5.527 |
OPV manufactured by Wyeth
OmniHib manufactured by Sanofi Pasteur
% R = in initially seronegative subjects, appearance of antibodies (titre 35 EL.U./mL); in initially seropositive subjects, at least maintenance of prevaccination titre
GMT = Geometric mean antibody titre
PT = Pertussis Toxoid
FHA = Filamentous Haemagglutinin
HBs = Hepatitis B surface (antigen)
V.R. = Vaccine Response (Vaccine response is defined as appearance of antibodies in initially seronegative subjects or as at least maintenance of pre-vaccination antibody titres in initially seropositive subjects.
Polio = Poliovirus
PRP = Polyribosyl-ribitol-phosphate
Clinical trials have investigated the tolerability and immunogenicity of the vaccine in various schedules (i.e. 2, 3, 4 months; 3, 4, 5 months; 2, 4, 6 months; 3, 5, 11 months; 1.5, 2.5, 3.5 months). Results obtained in all of the clinical studies for each of the components are summarized below:
DTaP component:
Immunological data:
One month after the 3-dose primary vaccination course, 98.5 to 100% of infants vaccinated with INFANRIX hexa had antibody titres of ≥ 0.1 IU/mL for both tetanus and diphtheria.
Following administration of a 4th dose of INFANRIX hexa in the second year of life, 100% of infants had antibody titres of ≥ 0.1 IU/mL for both tetanus and diphtheria.
One month after the 3-dose primary vaccination course, the overall response rate for each of the 3 individual pertussis antigens (PT, FHA, and pertactin) was between 97.2-99.3%, 95.2-100% and 95.9-99.3%, respectively.
Following administration of a 4th dose of INFANRIX hexa in the second year of life, a booster response was seen in at least 97.2%, 94.1%, and 100% of vaccinated infants against the respective pertussis antigens. Since a serological correlation for protection against pertussis disease does not exist, the efficacy of the pertussis component presently relies on efficacy trials described below.
Protective efficacy data:
The protective efficacy of the DTaP component, against WHO-defined typical pertussis (≥ 21 days of paroxysmal cough) was demonstrated after 3 dose primary immunization in the studies tabulated below in Table 4.
Table 4 - Protective efficacy data after 3 dose primary immunization
| Study | Country | Schedule | Vaccine efficacy | Considerations |
|---|---|---|---|---|
| Household contact study (prospective blinded) | Germany | 3,4,5 months | 88.7% | Based on data collected from secondary contacts in households where there was an index case with typical pertussis. |
| Efficacy study (NIH sponsored) | Italy | 2,4,6 months | 84% | In a follow-up of the same cohort, the efficacy was confirmed up to 60 months after completion of primary vaccination without administration of a booster dose of pertussis. |
Hepatitis B component:
After the primary vaccination course with INFANRIX hexa, 98.5 to 100% of infants developed protective antibody titres of ≥ 10 mIU/mL.
At one month after the booster dose, administered 18 months after primary vaccination, 97 to 100% of these subjects had protective titres of ≥ 10 mIU/mL.
IPV component:
One month after the primary vaccination, the seroprotection rates for each of the three serotypes (types 1, 2, and 3) were 99.2 to 100%, 94.5 to 99.0%, and 98.8 to 100%, respectively.
Following administration of the booster dose, at least 98.5%, 98.5%, and 100% of infants were seroprotected for the three serotypes, respectively.
Hib component:
One month after completion of the primary vaccination course, the Geometric Mean Concentration (GMC) of antibodies ranged from 1.52 to 3.53 mcg/mL, with between 93.5 and 100% of the subjects reaching antibody titres ≥ 0.15 mcg/mL.
One month after the booster dose given in the second year of life, the GMC ranged from 19.1 to 94.0 mcg/mL, with 99.5 to 100% of the subjects reaching antibody titres ≥ 0.15 mcg/mL.
These GMCs are numerically lower when compared to GMCs resulting from separate administration of the Hib component, however they are not different from those elicited by comparator vaccines DTaP-Hib and DTaP-IPV-Hib vaccines.
Induction of immunological memory has been shown to be an important and intrinsic part of the protective immune response following administration of Hib conjugate vaccines. Children primed with INFANRIX hexa had an anamnestic response (defined as a rapid and substantial increase in antibody level) on subsequent exposure to the antigen.
Immunogenicity in preterm infants (3 Dose Primary Series)
One month after 3-dose primary vaccination at least 98.7% of subjects were seroprotected against diphtheria, tetanus and poliovirus types 1 and 2; at least 90.9% had seroprotective antibody levels against the hepatitis B, PRP and poliovirus type 3 antigens; and all subjects were seropositive for antibodies against FHA and PRN while 94.9% were seropositive for anti-PT antibodies.
One month after the booster dose at least 98.4% of subjects had seroprotective or seropositive antibody levels against each of the antigens except against PT (at least 96.8%) and hepatitis B (at least 88.7%). The response to the booster dose in terms of fold increases in antibody concentrations (15- to 235-fold), indicate that preterm infants were adequately primed for all the antigens of INFANRIX hexa.
In a follow-up study involving 74 preterm infants, approximately 2.5 to 3 years after the booster dose, 85.3% of the children were still seroprotected against hepatitis B and at least 95.7% were seroprotected against the three poliovirus types and PRP.
Post-marketing experience:
The effectiveness of the Hib component of INFANRIX hexa was investigated via an extensive post-marketing surveillance study conducted in Germany. Over a seven year follow-up period, the effectiveness of the Hib components of two hexavalent vaccines, of which one was INFANRIX hexa, was 89.6% for a 3-dose full primary series and 100% for a 3-dose full primary series plus booster dose (irrespective of the Hib vaccine used for priming).
Persistence of the immune response:
The persistence of the immune response to a 3-dose primary and booster schedule with INFANRIX hexa was evaluated in children 4-8 years of age. Protective immunity against the three poliovirus types and PRP was observed in at least 91.0% of children and against diphtheria and tetanus in at least 64.7% of children. At least 25.4% (anti-PT), 97.5% (anti-FHA) and 87.0% (anti-PRN) of children were seropositive against the pertussis components.
With regards to hepatitis B, seroprotective antibody concentrations following a 3-dose primary and booster schedule with INFANRIX hexa have been shown to persist in ≥ 85% (82.3-88.7% CI 95%) of subjects 4-5 years of age, in ≥ 72% (70.0-78.0% CI 95%) of subjects 7-8 years of age, in ≥60% (54.6-66.1% CI 95%) of subjects 12-13 years of age and in 53.7% (47.6-59.8% CI 95%) of subjects 14-15 years of age. Additionally, following a 2-dose primary and booster schedule, seroprotective antibody concentrations against hepatitis B persisted in ≥ 48% (38.0-58.9% CI 95%) of subjects 11-12 years of age.
Hepatitis B immunological memory was confirmed in children 4 to 15 years of age. These children had received INFANRIX hexa as primary and booster vaccination in infancy, and when an additional dose of monovalent HBV vaccine was administered, protective immunity was observed in at least 93% (89.6-96.0% CI 95%) of subjects.
Immune Response to INFANRIX hexa Administered as a 2 Dose Primary Series
After a complete vaccination according to a 2-dose primary and booster schedule with INFANRIX hexa, at least 97.9% of the subjects had developed seroprotective or seropositive antibody levels against each of the vaccine antigens (see Table 5).
Table 5 - Percentage of subjects with antibody titres ≥ assay cut-off and GMC/GMT one month after 2-dose primary (Post-dose 2) and one month after booster (Post-dose 3) vaccination with INFANRIX hexa
Antibody (cut-off) | Vaccination at 2-4-12 months | |||||||
Post-dose 2 N=223 (1 study) | Post-dose 3 N=196 (1 study) | |||||||
| % | % | |||||||
| Anti-diphtheria (0.1 IU/ml) † | 99.6 | 100.0 | ||||||
| GMC | 1.197 | 5.307 | ||||||
| Anti-tetanus (0.1 IU/ml) † | 100 | 100.0 | ||||||
| GMC | 1.380 | 4.720 | ||||||
| Anti-PT (5 EL.U/ml) | 100 | 99.5 | ||||||
| GMC | 49.3 | 86.1 | ||||||
| Anti-FHA (5 EL.U/ml) | 100 | 100.0 | ||||||
| GMC | 172.3 | 451.2 | ||||||
| Anti-PRN (5 EL.U/ml) | 99.6 | 100.0 | ||||||
| GMC | 74.5 | 242.9 | ||||||
| Anti-HBs (10 mIU/ml) † | 99.5 | 99.8 | ||||||
| GMC | - | - | ||||||
| Anti-Polio type 1 (1/8 dilution) † | 89.6 | 98.4 | ||||||
| GMT | 28.3 | 313.7 | ||||||
| Anti-Polio type 2 (1/8 dilution) † | 85.6 | 98.4 | ||||||
| GMT | 25.1 | 429.2 | ||||||
| Anti-Polio type 3 (1/8 dilution) † | 92.8 | 97.9 | ||||||
| GMT | 62.2 | 541.9 | ||||||
| Anti-PRP (0.15 μg/ml) † | 84.3 | 100.0* | ||||||
| GMC | 0.671 | 13.737 | ||||||
N=number of subjects
* Post booster, 94.4% of subjects in the 2-4-12 months schedule had anti-PRP
concentration ≥ 1 μg/ml indicative of long-term protection.
† cut-off accepted as indicative of protection
Immunogenicity in infants and toddlers born to mothers vaccinated with Tdap (BOOSTRIX) during pregnancy
In two clinical studies (DTPA-048, -049), more than 500 infants and toddlers, born to mothers vaccinated with BOOSTRIX or placebo after 27 weeks of pregnancy, received primary and booster vaccination of INFANRIX hexa and Prevnar* 13. Antibody response to diphtheria, tetanus, hepatitis B, inactivated polio virus, Haemophilus influenzae type b or pneumococcal antigens were comparable between infants/toddlers born to vaccinated mothers and infants/toddlers born to unvaccinated mothers. Lower concentrations of antibodies against all pertussis antigens (PT, FHA and PRN) were observed post primary vaccination and against PT and FHA antigens post booster vaccination in infants/toddlers born to vaccinated mothers compared to infants/toddlers born to unvaccinated mothers. However, 92.1% to 98.1% of subjects born to vaccinated mothers showed a booster response (post-booster antibody concentration ≥2 times the pre-booster antibody concentration) against these pertussis antigens.
*Trademark owned by Wyeth LLC