


Product Monograph - Inspiolto Respimat
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Nonmedicinal Ingredients |
| oral inhalation | Inhalation Solution/ Each actuation delivers 2.5 mcg tiotropium (as tiotropium bromide monohydrate) and 2.5 mcg olodaterol (as olodaterol hydrochloride) from the mouthpiece. | Benzalkonium chloride, disodium edetate, purified water and hydrochloric acid. |
INDICATIONS AND CLINICAL USE
INSPIOLTO RESPIMAT (tiotropium bromide monohydrate and olodaterol hydrochloride) is a combination of a long-acting muscarinic antagonist (LAMA) and a long-acting beta2-adrenergic agonist (LABA) indicated for the long term, once daily maintenance bronchodilator treatment of airflow obstruction in patients with Chronic Obstructive Pulmonary Disease (COPD), including chronic bronchitis and emphysema.
INSPIOLTO RESPIMAT is not indicated for the relief of acute deterioration of COPD.
INSPIOLTO RESPIMAT is not indicated for asthma use. The safety and effectiveness of INSPIOLTO RESPIMAT in asthma have not been established (see CONTRAINDICATIONS and WARNINGS AND PRECAUTIONS, General).
Geriatrics (> 65 years of age):
Elderly patients can use INSPIOLTO RESPIMAT at the recommended dose. No dosage adjustment is required.
Pediatrics (< 18 years of age):
INSPIOLTO RESPIMAT should not be used in patients under 18 years of age.
CONTRAINDICATIONS
INSPIOLTO RESPIMAT (tiotropium bromide monohydrate and olodaterol hydrochloride) is contraindicated in patients with hypersensitivity to tiotropium bromide monohydrate or olodaterol hydrochloride or to any of the excipients (see DOSAGE FORM COMPOSTION AND PACKAGING SECTION).
INSPIOLTO RESPIMAT is also contraindicated in patients with a history of hypersensitivity to atropine or its derivatives, e.g. ipratropium.
All LABA are contraindicated in patients with asthma without use of a long-term asthma control medication (see WARNINGS AND PRECAUTIONS). INSPIOLTO RESPIMAT is not indicated for the treatment of asthma.
WARNINGS AND PRECAUTIONS
WARNING: ASTHMA-RELATED DEATH Long-acting beta2-adrenergic agonists (LABA) increase the risk of asthma-related death. Data from a large, placebo-controlled US study that compared the safety of another long-acting beta2-adrenergic agonist (salmeterol) to placebo added to patients’ usual asthma therapy, showed an increase in asthma-related deaths in patients receiving salmeterol. This finding with salmeterol is considered a class effect of LABA, including olodaterol, one of the active ingredients in INSPIOLTO RESPIMAT. INSPIOLTO RESPIMAT is only indicated for COPD. The safety and efficacy of INSPIOLTO RESPIMAT in patients with asthma have not been established. INSPIOLTO RESPIMAT is not indicated for the treatment of asthma. |
General
INSPIOLTO RESPIMAT should not be used more frequently than once daily.
Not for use in asthma
INSPIOLTO RESPIMAT is only indicated for COPD. INSPIOLTO RESPIMAT should not be used in asthma due to the absence of long-term safety and efficacy data in asthma with INSPIOLTO RESPIMAT.
It has been shown that long-acting beta2-adrenergic agonists may increase the risk of asthma-related death. Data from a 28-week, large placebo-controlled US study comparing the safety of a twice-daily long-acting beta2-adrenergic agonist (salmeterol) with placebo, each added to usual asthma therapy, showed an increase in asthma-related deaths in patients receiving salmeterol (13 out of 13,176 in patients treated with salmeterol vs. 3 out of 13,179 in patients treated with placebo; RR 4.37, 95% CI 1.25, 15.34). The increased risk of asthma related death may represent a class effect of the long-acting beta2-adrenergic agonists, including olodaterol, one of the active ingredients of INSPIOLTO RESPIMAT. No study adequate to determine whether the rate of asthma-related death is increased in patients treated with INSPIOLTO RESPIMAT has been conducted.
Acute bronchospasm
INSPIOLTO RESPIMAT is not indicated for the treatment of acute episodes of bronchospasm, i.e. as rescue therapy. INSPIOLTO RESPIMAT has not been studied in the relief of acute symptoms and extra doses should not be used for that purpose. Acute symptoms should be treated with an inhaled short-acting beta2-agonist. INSPIOLTO RESPIMAT should not be initiated in patients with acutely deteriorating COPD, which may be a life-threatening condition. The use of INSPIOLTO RESPIMAT in this setting is inappropriate.
When prescribing INSPIOLTO RESPIMAT, the healthcare professional should also provide the patient with an inhaled, short-acting bronchodilator for treatment of COPD symptoms that occur acutely, despite regular once-daily use of INSPIOLTO RESPIMAT.
When beginning treatment with INSPIOLTO RESPIMAT, patients who have been taking inhaled, short-acting bronchodilators on a regular basis (e.g. four times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms.
COPD may deteriorate acutely over a period of hours or chronically over several days or longer. If INSPIOLTO RESPIMAT no longer controls the symptoms of bronchoconstriction, or the patient’s inhaled, short-acting beta2-agonist becomes less effective or the patient needs more inhalation of short-acting beta2-agonist than usual, these may be markers of deterioration of disease. In this setting, a re-evaluation of the patient and the COPD treatment regimen should be undertaken at once. Increasing the daily dosage of INSPIOLTO RESPIMAT beyond the recommended dose is not appropriate in this situation.
Excessive Use and Use with other LABA and LAMA products
As with other inhaled bronchodilators, INSPIOLTO RESPIMAT should not be used more often or at higher doses than recommended. INSPIOLTO RESPIMAT should not be administered concomitantly with other medicines containing long-acting beta2-adrenergic agonists, short- or long-acting muscarinic antagonists (e.g. ipratropium, tiotropium, glycopyrronium, aclidinium, umeclidinium), as an overdose may result (see DRUG INTERACTIONS).
Effects on Ability to Drive or Use Machines
There have been no studies investigating the effect of INSPIOLTO RESPIMAT on the ability to perform tasks that require judgement, motor or cognitive skills. The occurrence of dizziness or blurred vision may influence the ability to drive or to use machinery.
Anticholinergic Effects
Like other anticholinergic drugs, INSPIOLTO RESPIMAT should be used with caution in patients with narrow-angle glaucoma or urinary retention.
Worsening of Narrow-Angle Glaucoma
INSPIOLTO RESPIMAT should be used with caution in patients with narrow-angle glaucoma. Patients should be cautioned to avoid getting the mist into their eyes. They should be advised that this may result in precipitation or worsening of narrow-angle glaucoma. Prescribers and patients should be alert for signs and symptoms of acute narrow-angle glaucoma (e.g. eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a physician immediately should any of these signs or symptoms develop. Miotic drops alone are not considered to be effective treatment.
Worsening of Urinary Retention
INSPIOLTO RESPIMAT should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of prostatic hyperplasia or bladder-neck obstruction (e.g. difficulty passing urine, painful urination). Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
Cardiovascular
INSPIOLTO RESPIMAT is a combination of a long-acting beta2-agonist (olodaterol) and a long-acting muscarinic antagonist (tiotropium). Cardiovascular effects, such as cardiac arrhythmias, e.g. atrial fibrillation and tachycardia, may be seen after the administration of sympathomimetic agents and muscarinic receptor antagonists, including INSPIOLTO RESPIMAT. In case such effects occur, treatment may need to be discontinued.
Clinically significant cardiovascular effects and fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs. Cardiovascular effects such as tachycardia, arrhythmia, palpitations, myocardial ischemia, angina pectoris, hypertension or hypotension have been associated with use of beta-adrenergic agonists. In addition, beta-adrenergic agonists have been reported to produce electrocardiogram (ECG) changes, such as flattening of the T wave, prolongation of the QTc interval, and ST segment depression. Therefore, INSPIOLTO RESPIMAT, like all products containing beta-adrenergic agonists, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, acute myocardial infarction, cardiac arrhythmias, hypertrophic obstructive cardiomyopathy and hypertension.
Heart Rate
Like other beta2-agonists, olodaterol may produce clinically significant cardiovascular effects in some patients as measured by an increase in pulse rate, systolic or diastolic blood pressure, or cardiac arrhythmias such as atrial fibrillation, supraventricular tachycardia and extrasystoles. If such effects occur, INSPIOLTO RESPIMAT may need to be discontinued.
QTc Interval
As with other beta2-agonists, caution is recommended if INSPIOLTO RESPIMAT is administered to patients with a known history of QTc prolongation, risk factors for torsade de pointes (e.g. hypokalemia), or patients who are taking medications known to prolong the QTc interval (see DRUG INTERACTIONS, Drugs known to prolong the QTc interval).
Hypokalemia
Beta2-adrenergic agonists may produce significant hypokalemia in some patients, which has the potential to produce adverse cardiovascular effects (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics). The decrease in serum potassium is usually transient, not requiring supplementation. INSPIOLTO RESPIMAT should be used with caution in patients predisposed to low levels of serum potassium. In patients with severe COPD, hypokalemia may be potentiated by hypoxia and concomitant treatment (see DRUG INTERACTIONS), which may increase the susceptibility to cardiac arrhythmias.
Clinically notable decreases in serum potassium were infrequent during clinical studies with long-term administration of INSPIOLTO RESPIMAT and with rates similar to either tiotropium or olodaterol.
Endocrine and Metabolism
Coexisting Conditions
INSPIOLTO RESPIMAT, like other medications containing sympathomimetic amines, should be used with caution in patients with convulsive disorders or thyrotoxicosis, and in patients who are unusually responsive to sympathomimetic amines. Doses of the related beta2-agonist salbutamol, when administered intravenously, have been reported to aggravate pre-existing diabetes mellitus and ketoacidosis.
Hyperglycemia
Inhalation of high doses of beta2-adrenergic agonists may produce increases in plasma glucose. Upon initiation of treatment with INSPIOLTO RESPIMAT plasma glucose should be monitored more closely in diabetic patients. INSPIOLTO RESPIMAT has not been investigated in patients whose diabetes mellitus is not controlled.
Respiratory
Benzalkonium Chloride
This medicine contains 0.0011 mg benzalkonium chloride in each actuation.
Benzalkonium chloride may cause wheezing and breathing difficulties (bronchospasm). Patients with asthma are at an increased risk for these adverse events.
Paradoxical Bronchospasm
As with other inhaled medicines INSPIOLTO RESPIMAT may result in paradoxical bronchospasm that may be life-threatening. If paradoxical bronchospasm occurs, INSPIOLTO RESPIMAT should be discontinued immediately and alternative therapy substituted.
Hypersensitivity
As with all medications, immediate hypersensitivity reactions may occur after administration of INSPIOLTO RESPIMAT.
If signs suggesting allergic reactions (in particular, difficulties in breathing or swallowing, swelling of tongue, lips and face, urticaria, skin rash) occur, INSPIOLTO RESPIMAT should be discontinued immediately and alternative therapy instituted. The patient should NOT be re-challenged with INSPIOLTO RESPIMAT (see CONTRAINDICATIONS).
Ophthalmologic
Worsening of Narrow-Angle Glaucoma (see WARNINGS AND PRECAUTIONS, Anticholinergic Effects).
Special Populations
Pregnant Women:
There is a limited amount of data from the use of tiotropium in pregnant women. For olodaterol no clinical data on exposed pregnancies are available.
Preclinical studies with tiotropium do not indicate direct or indirect harmful effects with respect to reproductive toxicity at clinically relevant doses.
Preclinical data for olodaterol revealed effects typical for beta-adrenergic agonists at high multiples of the therapeutic doses (see TOXICOLOGY).
INSPIOLTO RESPIMAT should be used during pregnancy only if the expected benefit to the mother justifies the potential risk to the fetus. Women should be advised to contact their physician if they become pregnant while taking INSPIOLTO RESPIMAT.
Labour and delivery:
There are no adequate and well-controlled human studies that have investigated the effects of tiotropium and olodaterol, alone or in combination, during labour and delivery. Because beta-agonists may potentially interfere with uterine contractility, INSPIOLTO RESPIMAT should be used during labour only if the potential benefit justifies the potential risk.
Nursing Women:
Clinical data from nursing women exposed to tiotropium and/or olodaterol are not available.
In animal studies both tiotropium and olodaterol and/or its metabolites have been detected in the milk of lactating rats, but it is not known whether tiotropium and/or olodaterol passes into human breast milk. Therefore, the use of INSPIOLTO RESPIMAT by breast-feeding women should only be considered if the expected benefit to the woman is greater than any possible risk to the infant.
Fertility:
Clinical data on fertility are not available for tiotropium and olodaterol or the combination of both components. Animal studies performed with the individual components tiotropium and olodaterol showed no indication of any adverse effect on fertility (see TOXICOLOGY).
Pediatrics (< 18 years of age):
INSPIOLTO RESPIMAT should not be used in patients under 18 years of age. The safety and effectiveness of INSPIOLTO RESPIMAT in the pediatric population have not been established.
Geriatrics (> 65 years of age):
Based on available data, no adjustment of INSPIOLTO RESPIMAT dosage in geriatric patients is necessary.
Hepatic Insufficiency:
INSPIOLTO RESPIMAT contains olodaterol, which is predominantly metabolized in the liver. Patients with mild and moderate hepatic impairment can use INSPIOLTO RESPIMAT at the recommended dose.
There are no data available for use of olodaterol in patients with severe hepatic impairment.
Renal Insufficiency:
As with all predominantly renally excreted drugs, INSPIOLTO RESPIMAT should be used only if the expected benefit outweighs the potential risk in patients with moderate to severe renal impairment (creatinine clearance of < 50 ml/min). These patients should be monitored closely for potential adverse drug reactions (see ACTION and CLINICAL PHARAMACOLOGY).
Monitoring and Laboratory Tests
Beta2-adrenergic agonists may produce significant hypokalemia in some patients, which has the potential to produce adverse cardiovascular effects (see ACTION AND CLINICAL PHARMACOLOGY, Pharmacodynamics). The decrease in serum potassium is usually transient, not requiring supplementation. In patients with severe COPD, hypokalemia may be potentiated by hypoxia and concomitant treatment (see DRUG INTERACTIONS), which may increase the susceptibility to cardiac arrhythmias. It is therefore recommended that serum potassium levels be monitored in patients predisposed to low levels of serum potassium.
Due to the hyperglycemic effect observed with other beta-agonists, additional blood glucose monitoring is recommended in diabetic patients.
Worsening of Urinary Retention (see WARNING and PRECAUTIONS, Anticholinergic Effects).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
Long-acting beta2-adrenergic agonists such as olodaterol, one of the active ingredients of INSPIOLTO RESPIMAT, increase the risk of asthma-related death. INSPIOLTO RESPIMAT is not indicated for the treatment of asthma (see BOXED WARNING and WARNING AND PRECAUTIONS).
INSPIOLTO RESPIMAT is a combination of a long-acting muscarinic antagonist and a long-acting beta2-adrenergic agonist. Adverse reactions to INSPIOLTO RESPIMAT are expected to be similar in nature to reactions to other muscarinic antagonists and beta2-agonists.
Adverse reactions to tiotropium are similar in nature to reactions to other anticholinergic bronchodilators and may include cardiovascular effects (atrial arrhythmias and tachycardia), ocular disorders (e.g. blurred vision), dysuria, urinary retention, gastrointestinal disorders (e.g. constipation and dry mouth), cough and immediate hypersensitivity reactions (urticaria, rash, bronchospasm, edema, angioedema, and anaphylactic shock or anaphylactic reaction). Many of the listed adverse reactions can be assigned to the anticholinergic properties of tiotropium bromide.
Adverse reactions that have been associated with other beta2-adrenergic agonists include: tachycardia, arrhythmia, palpitations, myocardial ischaemia, angina pectoris, hypertension or hypotension, tremor, headache, nervousness, insomnia, dizziness, dry mouth, nausea, muscle spasms, fatigue, malaise, hypokalemia, hyperglycemia, metabolic acidosis and immediate hypersensitivity reactions.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The clinical program for INSPIOLTO RESPIMAT included 7151 subjects with COPD in two 52-week active-controlled trials, one 12-week placebo-controlled trial, three 6-week placebo-controlled cross-over trials, and four additional trials of shorter duration. A total of 1988 subjects received at least 1 dose of INSPIOLTO RESPIMAT. Adverse reactions observed in the ≤12-week trials were consistent with those observed in the 52-week trials which formed the primary safety database.
The primary safety database consisted of pooled data from the two 52-week double-blind, active-controlled, parallel group confirmatory clinical trials. These trials included 5162 adult COPD patients (72.9% males and 27.1% females) 40 years of age and older. Of these patients, 1029 were treated with INSPIOLTO RESPIMAT once daily. The INSPIOLTO RESPIMAT group was composed of mostly Caucasians (71.1%) with a mean age of 63.8 years and a mean percent predicted FEV1 at baseline of 43.2%. In these two trials tiotropium 5 mcg and olodaterol 5 mcg were included as active control arms and no placebo was used.
In these two clinical trials 74% of patients exposed to INSPIOLTO RESPIMAT reported an adverse reaction compared to 76.6% and 73.3% in the olodaterol 5 mcg and tiotropium 5 mcg groups, respectively. The proportion of patients who discontinued due to an adverse reaction was 7.4% for INSPIOLTO RESPIMAT treated patients compared to 9.9% and 9.0% for olodaterol 5 mcg and tiotropium 5 mcg treated patients. The adverse reaction most commonly leading to discontinuation was worsening COPD.
Table 1 shows all adverse reactions that occurred with an incidence of ≥1% in the INSPIOLTO RESPIMAT treatment group.
Table 1: Adverse drug reactions equal to or greater than (≥)1% in COPD patients exposed to INSPIOLTO RESPIMAT: Pooled data from the two 52-week, double-blind, active-controlled clinical trials in COPD patients 40 years of age and older
| Treatment | INSPIOLTO RESPIMAT (once daily) n = 1029 n (%) | Tiotropium 5 mcg (once daily) n = 1033 n (%) | Olodaterol 5 mcg (once daily) n = 1038 n (%) |
Body system (adverse drug reaction) | |||
| Infections and infestations | |||
| Nasopharyngitis | 128 (12.4) | 121 (11.7) | 131 (12.6) |
| Upper respiratory tract infection | 54 (5.2) | 57 (5.5) | 56 (5.4) |
| Bronchitis | 31 (3.0) | 23 (2.2) | 33 (3.2) |
| Urinary tract infection | 22 (2.1) | 30 (2.9) | 13 (1.3) |
| Sinusitis | 21 (2.0) | 13 (1.3) | 18 (1.7) |
| Oropharyngeal candidiasis | 11 (1.1) | 4 (0.4) | 10 (1.0) |
| Nervous system disorders | |||
| Dizziness | 18 (1.7) | 16 (1.5) | 14 (1.3) |
| Vascular disorders | |||
| Hypertension | 30 (2.9) | 30 (2.9) | 48 (4.6) |
| Respiratory, thoracic and mediastinal disorders | |||
| Cough | 40 (3.9) | 45 (4.4) | 31 (3.0) |
| Oropharyngeal pain | 10 (1.0) | 16 (1.5) | 17 (1.6) |
| Dysphonia | 10 (1.0) | 11 (1.1) | 9 (0.9) |
| Gastrointestinal disorders | |||
| Diarrhea | 24 (2.3) | 27 (2.6) | 33 (3.2) |
| Constipation | 13 (1.3) | 16 (1.5) | 16 (1.5) |
| Dry mouth (usually mild) | 16 (1.6) | 19 (1.8) | 10 (1.0) |
| General disorders and administration site conditions | |||
| Edema peripheral | 14 (1.4) | 16 (1.5) | 15 (1.4) |
| Fatigue | 11 (1.1) | 8 (0.8) | 13 (1.3) |
| Musculoskeletal and connective tissue disorders | |||
| Back pain | 37 (3.6) | 19 (1.8) | 35 (3.4) |
| Arthralgia | 18 (1.7) | 13 (1.3) | 14 (1.3) |
Less Common Clinical Trial Adverse Drug Reactions (<1%)
Infections and infestations: Lower respiratory tract infection
Metabolism and nutrition disorders: Dehydration
Nervous system disorders: Insomnia
Eye disorders: Intraocular pressure increased, Glaucoma, Vision blurred
Cardiac disorders: Palpitations, Tachycardia, Atrial fibrillation, Supraventricular tachycardia, Ventricular extrasystoles
Respiratory, thoracic and mediastinal disorders: Epistaxis, Pharyngitis, Laryngitis, Bronchospasm
Gastrointestinal disorders: Stomatitis, Gingivitis, Glossitis, Dysphagia, Gastroesophageal reflux disease, Intestinal obstruction including ileus paralytic
Skin and subcutaneous disorders: Rash, Pruritus, Urticaria, Skin infection, Skin ulcer, Dry skin, Hypersensitivity (including immediate reactions) and Angioedema
Musculoskeletal and connective tissue disorders: Joint swelling, Myalgia, Muscle spasms
Renal and urinary disorders: Urinary retention (usually in men with predisposing factors), Dysuria
General disorders and administration site conditions: Asthenia
Investigations: Electrocardiogram QT prolonged
Many of the listed undesirable effects can be assigned to either the anticholinergic properties of tiotropium or to the ß-adrenergic properties of olodaterol, the components of INSPIOLTO RESPIMAT.
Post-Market Adverse Drug Reactions
Currently, there is no evidence from post-market data for additional adverse drug reactions for INSPIOLTO RESPIMAT beyond those listed in the Clinical Trial Adverse Drug Reactions section.
The following adverse reactions have been identified during the worldwide use of SPIRIVA® RESPIMAT® and another tiotropium formulation, SPIRIVA® HandiHaler® (tiotropium bromide inhalation powder) Capsules for Oral Inhalation: Eye disorders: glaucoma, intraocular pressure increased, vision blurred; Cardiac disorder: atrial fibrillation, tachycardia, supraventricular tachycardia; Respiratory disorders: bronchospasm; Gastrointestinal disorders: glossitis, stomatitis; Metabolism and nutrition disorders: dehydration; Nervous system disorders: insomnia; Skin and immune system disorders: hypersensitivity (including immediate reactions), urticaria. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
DRUG INTERACTIONS
Drug-Drug Interactions
Drug-drug interaction studies have been conducted with the mono components olodaterol and tiotropium. No specific drug-interaction studies were conducted for INSPIOLTO RESPIMAT.
Tiotropium is mainly excreted renally (approximately 74% of the intravenously administered dose). The remaining dose is mainly nonenzymatically cleared with a minor portion (<20% of intravenous dose) being metabolized by CYP2D6 and CYP3A4 (see METABOLISM). Tiotropium does not inhibit cytochrome P450 1A1, 1A2, 2B6, 2C9, 2C19, 2D6, 2E1, 3A4 even in supratherapeutic concentrations, which makes clinically relevant metabolic interactions with tiotropium unlikely.
Although no formal drug interaction studies have been performed, in clinical studies, INSPIOLTO RESPIMAT has been used concomitantly with other drugs commonly used to treat COPD including short-acting beta-adrenergic agonists, methylxanthines, and oral and inhaled corticosteroids. No safety findings were observed to contraindicate administration of these agents with INSPIOLTO RESPIMAT.
The chronic co-administration of tiotropium bromide with other anticholinergic-containing drugs has not been studied. Therefore, the chronic co-administration of other anticholinergic drugs with INSPIOLTO RESPIMAT is not recommended.
Drugs known to prolong QTc interval
INSPIOLTO RESPIMAT, as other beta2-adrenergic agonist-containing drugs, should be administered with caution to patients being treated with monoamine oxidase inhibitors, tricyclic antidepressants, or drugs known to prolong the QT interval, as any effect of these on the QT interval may be potentiated. Drugs known to prolong the QT-interval may increase the risk of ventricular arrhythmia (see WARNINGS AND PRECAUTIONS and ACTION AND CLINICAL PHARMACOLOGY).
Sympathomimetic Agents
Concomitant administration of other sympathomimetic agents (alone or as part of combination therapy) may potentiate the undesirable effects of INSPIOLTO RESPIMAT (see WARNINGS AND PRECAUTIONS).
Treatments leading to Hypokalemia
Beta2-adrenoceptor agonists have been associated with reductions in serum potassium levels. Concomitant treatment with xanthine derivatives, steroids, or non-potassium sparing diuretics may potentiate any hypokalemic effect of adrenergic agonists (see WARNINGS AND PRECAUTIONS, Hypokalemia).
Beta- adrenergic Blockers
Beta-adrenergic blockers may weaken or antagonise the effect of olodaterol. Therefore, INSPIOLTO RESPIMAT should not be given together with beta-adrenergic blockers (including eye-drops) unless there are compelling reasons for their use. In this setting, cardioselective beta-blockers could be considered, although they should be administered with caution.
Pharmacokinetic Drug-Drug Interactions
In a drug interaction study with olodaterol using the strong dual CYP and P-gp inhibitor ketoconazole a 1.7-fold increase of systemic exposure to olodaterol was observed. No safety concerns were identified in clinical studies of up to one year with olodaterol at doses up to twice the recommended therapeutic dose. No dose adjustment of INSPIOLTO RESPIMAT is necessary.
Drug-Drug Interactions
Drug-drug interaction studies with olodaterol were carried out using fluconazole as model inhibitor of CYP 2C9 and ketoconazole as a strong P-gp and CYP3A inhibitor.
Table 2: Established or Potential Drug-Drug Interactions
| Drug | Ref | Effect | Clinical comment |
|---|---|---|---|
Fluconazole (inhibitor of CYP 2C9) | CT | Co-administration of 400 mg fluconazole once daily for 14 days had no relevant effect on systemic exposure to olodaterol. | No dose adjustment is necessary. |
Ketoconazole (P-gp and CYP inhibitor) | CT | Co-administration of 400 mg ketoconazole once daily for 14 days increased olodaterol Cmax by 66% and AUC0-1 by 68%. | No dose adjustment is necessary. Caution may be warranted with concomitant therapy. |
| P-gp Inhibitors | T | Co-administration may lead to increased olodaterol Cmax and AUC0-1. | No dose adjustment is necessary. Caution may be warranted with concomitant therapy. |
| Legend: CT = Clinical Trial; T = Theoretical | |||
Drug-Food Interactions
No food interaction study was conducted because any possible food effects on olodaterol and tiotropium systemic exposure are considered to be of no relevance for efficacy, tolerability and safety.
Drug-Lifestyle Interactions
No studies on the effects on the ability to drive and use machines have been performed.
However, patients should be advised that dizziness and blurred vision have been reported with the use of INSPIOLTO RESPIMAT. Therefore, caution should be recommended when driving a car or operating machinery. If patients experience such symptoms, they should avoid potentially hazardous tasks such as driving or operating machinery.
DOSAGE AND ADMINISTRATION
Dosing Considerations
- Counselling by doctors on smoking cessation should be the first step in treating patients with COPD who smoke, independent of the clinical presentation i.e. chronic bronchitis (with or without airflow limitation) or emphysema. Cessation of smoking produces dramatic symptomatic benefits and has been shown to confer a survival advantage.
- As with other inhaled drugs containing beta2-adrenergic agents, INSPIOLTO RESPIMAT should not be used more often than recommended, at higher doses than recommended, or in conjunction with other medicines containing a long-acting beta-adrenergic agonist or a long-acting muscarinic antagonist, as an overdose may result.
- When beginning treatment with INSPIOLTO RESPIMAT, patients who have been taking oral or inhaled, short-acting beta2-agonists on a regular basis (e.g. 4 times a day) should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief of acute respiratory symptoms.
- Patients should be made aware that for optimum benefit, INSPIOLTO RESPIMAT must be used regularly, even when asymptomatic.
Recommended Dose and Dosage Adjustment
The recommended dose for adults is 5 mcg tiotropium and 5 mcg olodaterol given as two inhalations from the RESPIMAT inhaler once daily, at the same time of the day.
The delivered dose is 2.5 mcg tiotropium and 2.5 mcg olodaterol per inhalation (2 inhalations comprise one medicinal dose).
Dosing in Special Populations
No dosage adjustment is required in patients over 65 years of age, patients with mild and moderate hepatic impairment, or renally impaired patients. However, as with all predominantly renally excreted drugs, INSPIOLTO RESPIMAT use should be monitored closely in patients with moderate to severe renal impairment.
INSPIOLTO RESPIMAT has not been studied in patients with severe hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY).
INSPIOLTO RESPIMAT should not be used in patients under 18 years of age.
Missed Dose
Patients should be advised that if they forget to take a dose, they should take one as soon as they remember. INSPIOLTO RESPIMAT should not be taken more than once per day (two inhalations/dose).
Administration
INSPIOLTO RESPIMAT should be administered once daily, at the same time of day, every day via inhalation through the RESPIMAT inhalation device only. To ensure proper administration of INSPIOLTO RESPIMAT, the doctor or other qualified health care professional should teach the patient how to operate the RESPIMAT inhalation device (see Part III CONSUMER INFORMATION).
OVERDOSAGE
Symptoms
Tiotropium:
High doses of tiotropium bromide may lead to signs and symptoms of exaggerated anticholinergic effects, such as constipation, voiding difficulties or increased intraocular pressure causing pain, vision disturbances or reddening of the eye.
No adverse events, beyond dry mouth/throat and dry nasal mucosa in a dose-dependent (10-40 mcg daily) incidence, were observed following 14-day dosing of up to 40 mcg tiotropium inhalation solution in healthy subjects with the exception of pronounced reduction in salivary flow from day 7 onwards.
Should signs of serious anticholinergic toxicity appear, vital signs should be carefully monitored and appropriate therapy should be initiated.
Olodaterol:
An overdose of olodaterol is likely to lead to exaggerated effects typical of beta2-adrenergic agonists, i.e. myocardial ischaemia, hypertension or hypotension, tachycardia, QTc prolongation, arrhythmias, palpitation, dizziness, nervousness, insomnia, anxiety, headache, tremor, dry mouth, muscle spasms, nausea, fatigue, malaise, hypokalemia, hyperglycemia and metabolic acidosis.
Treatment of Overdose
Treatment with INSPIOLTO RESPIMAT should be discontinued. Supportive and symptomatic treatment is indicated. Serious cases should be hospitalised. Electrocardiogram monitoring is recommended in the event of overdosage. Use of cardioselective beta-blockers may be considered, but only subject to extreme caution since the use of beta-adrenergic blocker medication may provoke bronchospasm.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Tiotropium:
Tiotropium is a long acting muscarinic receptor antagonist (LAMA), also known as an anticholinergic. It has a similar affinity to the subtypes of muscarinic receptors M1 to M5. In the lungs, inhibition of M3-receptors at the smooth muscle results in relaxation of the airways. The competitive and reversible nature of antagonism was shown with human and animal origin receptors and isolated organ preparations. Tiotropium bromide is a quaternary ammonium molecule with duration of action sufficient to provide 24 hours of bronchoprotection with once-a-day inhalational administration.
The long duration of action of tiotropium is thought to be due to its slow dissociation kinetics from the muscarinic M3-receptor subtype. Dissociation from M2-receptors is faster than from M3, which in functional in vitro studies, elicited (kinetically controlled) receptor subtype selectivity of M3 over M2. As an N-quaternary anticholinergic, tiotropium is topically selective when administered by inhalation to the lung. Pharmacological in vitro and in vivo studies profiled tiotropium as a potent, long acting bronchodilator suitable for a once-daily dose regimen.
Olodaterol:
Olodaterol has a high affinity and high selectivity to the human beta2-adrenoceptor.
In vitro studies have shown that olodaterol has more than 241-fold greater agonist activity at beta2-adrenoceptors compared to beta1-adrenoceptors and 2299-fold greater agonist activity compared to beta3-adrenoceptors.
The compound exerts its pharmacological effects by binding and activation of beta2-adrenoceptors after topical administration by inhalation.
Activation of these receptors in the airways results in a stimulation of intracellular adenyl cyclase, an enzyme that mediates the synthesis of cyclic-3’, 5’ adenosine monophosphate (cAMP). Elevated levels of cAMP induce bronchodilation by relaxation of airway smooth muscle cells.
Olodaterol has the pre-clinical profile of a long-acting selective beta2-adrenoceptor agonist (LABA) with a fast onset of action and a duration of action of at least 24 hours.
Beta-adrenoceptors are divided into three subtypes, beta1-adrenoceptors predominantly expressed on cardiac smooth muscle, beta2-adrenoceptors predominantly expressed on airway smooth muscle and beta3-adrenoceptors predominantly expressed on adipose tissue. Beta2-agonists cause bronchodilation. Although the beta2-adrenoceptor is the predominant adrenergic receptor in the airway smooth muscle it is also present on the surface of a variety of other cells, including lung epithelial and endothelial cells and in the heart. The precise function of beta2-receptors in the heart is not known, but their presence raises the possibility that even highly selective beta2-adrenergic agonists may have cardiac effects.
Pharmacodynamics
Tiotropium
Primary Pharmacodynamic Effects
The primary pharmacodynamic effect in subjects with COPD following inhalation of tiotropium is bronchodilation, which is primarily a site-specific, rather than a systemic effect. Tiotropium bromide, administered once daily in the COPD population, provided significant improvement in lung function (forced expiratory volume in one second, FEV1 and forced vital capacity, FVC) within 30 minutes following the first dose which was maintained for 24 hours. Pharmacodynamic steady state was reached within one week with the majority of bronchodilation observed by the third day. Repeated inhalation of SPIRIVA RESPIMAT has not been linked with tolerance towards the bronchodilatory effects of the drug. Bronchodilatory effects gradually returned to baseline levels upon cessation of treatment with no evidence of rebound.
Secondary Pharmacodynamic Effects
Cardiac Electrophysiology:
In a multicenter, randomized, double-blind trial using tiotropium dry powder for inhalation that enrolled 198 patients with COPD, the number of subjects with changes from baseline-corrected QT interval of 30 to 60 msec was higher in the tiotropium group as compared with placebo. This difference was apparent using both the Bazett (QTcB) [20 (20%) patients vs., 12 (12%) patients] and Fredericia (QTcF) [16 (16%) patients vs. 1 (1%) patient] corrections of QT for heart rate. No patients in either group had either QTcB or QTcF of >500 msec. Other clinical trials with tiotropium did not detect an effect of the drug on QTc intervals.
The effect of tiotropium dry powder for inhalation on QT interval was also evaluated in a randomized, placebo- and positive-controlled crossover study in 53 healthy volunteers. Subjects received tiotropium inhalation powder 18 mcg, 54 mcg (3 times the recommended dose), or placebo for 12 days. ECG assessments were performed at baseline and throughout the dosing interval following the first and last dose of study medication. Relative to placebo, the maximum mean change from baseline in study-specific QTc interval was 3.2 msec and 0.8 msec for tiotropium inhalation powder 18 mcg and 54 mcg, respectively. No subject showed a new onset of QTc >500 msec or QTc changes from baseline of ≥60 msec.
Olodaterol:
The effect of olodaterol on ECG parameters was investigated in 24 healthy volunteers in a double-blind, randomised, placebo- and active (moxifloxacin) controlled, 6-way crossover study. Olodaterol was studied at single supratherapeutic doses of 10, 20, 30 and 50 mcg.
At the 10 mcg dose, no statistically significant effects on the QTc interval, QRS duration, PR interval, or heart rate were observed.
At the 20 to 50 mcg doses, increases in the *QTcN interval were observed that were maximal at 40 min post-dosing. At the 40 min time point, the placebo-adjusted mean time-matched changes from baseline in QTcN [ms] were 0.9 (90% CI -2.3, 4.1) at the 10 mcg dose, 6.1 (90% CI 2.9, 9.3) at the 20 mcg dose, 7.4 (90% CI 4.1, 10.7) at the 30 mcg dose, and 7.9 (90% CI 4.7, 11.1) at the 50 mcg dose.
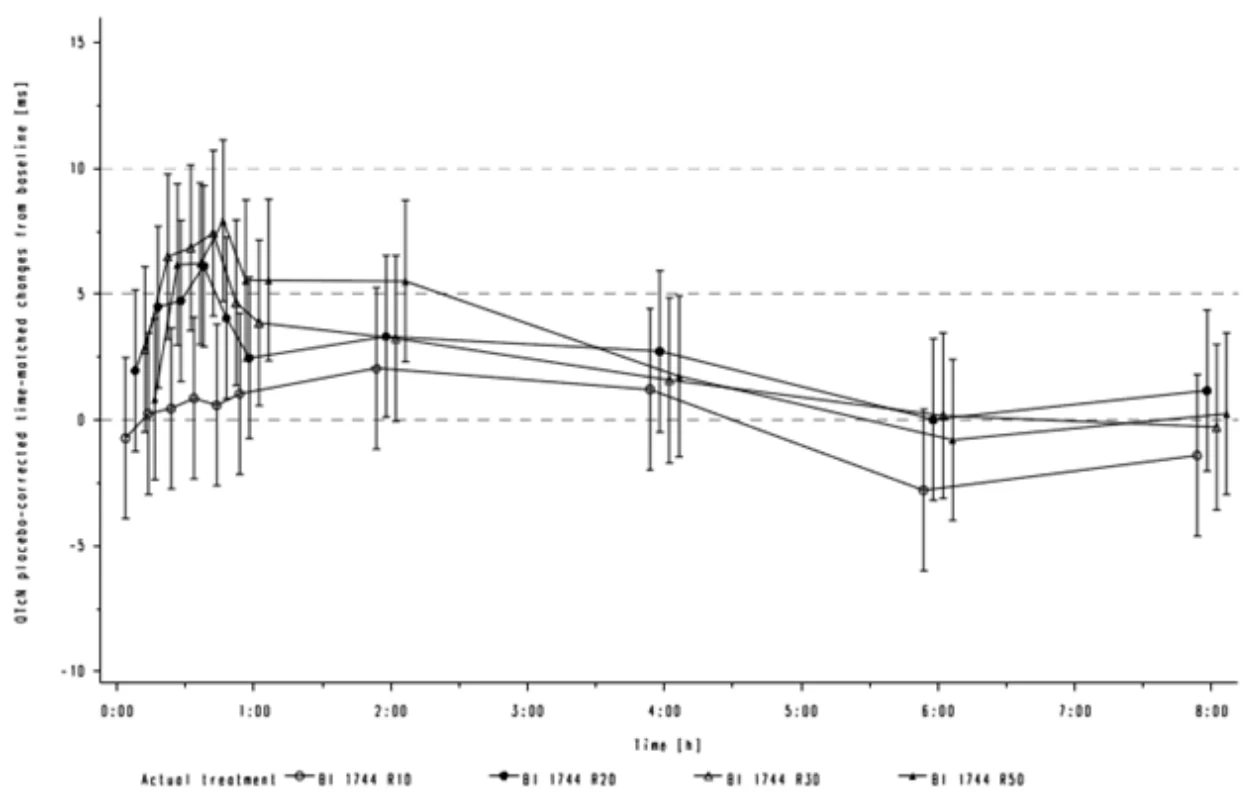
*QTcN=QT/RR0.21 (population heart rate-corrected QT interval)
At the 20 to 50 mcg doses, dose-dependent increases in heart rate were observed that were maximal at 20 min post-dosing. At the 20 min time point, the placebo-adjusted mean time-matched changes from baseline in heart rate [bpm] were 1.1 (90% CI -0.9, 3.1) at 10 mcg, 2.4 (90% CI 0.4, 4.4) at 20 mcg, 6.1 (90% CI 4.1, 8.2) at 30 mcg, and 8.4 (6.4, 10.4) at 50 mcg.
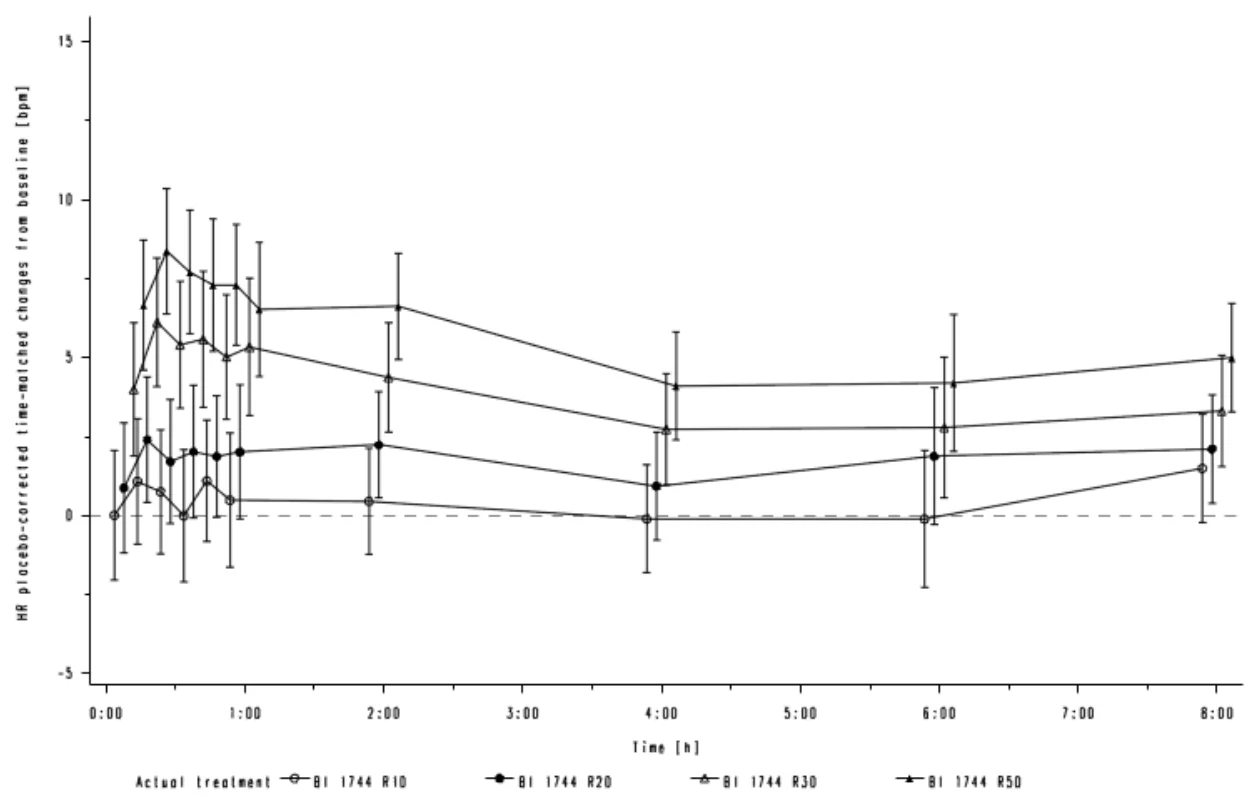
Cmax values for the 10 mcg, 20 mcg, 30 mcg, and 50 mcg single doses in this study were 3.3 pg/mL, 5.3 pg/mL, 9.6 pg/mL, and 16.2 pg/mL, respectively. The Cmax for the 5 mcg therapeutic dose at steady-state in patients with COPD is expected to average 4 pg/mL.
The effect of 5 mcg and 10 mcg olodaterol on heart rate and rhythm was assessed using continuous 24-hour ECG recording (Holter monitoring) in a subset of 772 patients in the 48-week, placebo-controlled Phase 3 Trials. There were no dose- or time-related trends or patterns observed for the magnitudes of mean changes in heart rate or premature beats. Shifts from baseline to the end of treatment in premature beats did not indicate meaningful differences between olodaterol 5 mcg, 10 mcg and placebo.
Tachyphylaxis
In the 48-week trials, the bronchodilator effects of olodaterol were maintained throughout the treatment period.
INSPIOLTO RESPIMAT
In two 52-week randomized, double-blind trials using INSPIOLTO RESPIMAT that enrolled 5162 patients with COPD, ECG assessments were performed post-dose on days 1, 85, 169, and 365. In a pooled analysis the number of subjects with changes from baseline-corrected QT interval of >30 msec using both the Bazett (QTcB) and Fredericia (QTcF), corrections of QT for heart rate ranged from 4.9-6.4% (QTcB) and 1.3-4.7% (QTcF) for the INSPIOLTO RESPIMAT group compared to
5.0-6.0% (QTcB) and 1.3-4.4% (QTcF) for olodaterol 5 mcg and 5.3-6.6% (QTcB) and 2.1-4.6% (QTcF) for tiotropium 5 mcg across the assessments conducted.
Pharmacokinetics
Table 3: Summary of Olodaterol and Tiotropium Pharmacokinetic Parameters
| Cmax (pg/mL) | t½ (h) | AUC (pg·h/mL) | Clearance (mL/min) | Volume of distribution (L) | ||||
|---|---|---|---|---|---|---|---|---|
| Tiotropium | ||||||||
| 13.9 (64.7) 1 | 27-452 | 69.4 (33.2)3 | 880 (22.1)4 | 2665 (27.8) 4 | ||||
| Olodaterol | ||||||||
| 4.39 (49.2)1 | 45.1 (36.0) 5 | 33.2 (66.1)3 | 872 (33.5) 6 | 1110 (29.5) 6 | ||||
1 Geometric mean (gCV%) maximum plasma concentration from COPD patients treated once daily for 4 weeks with INSPIOLTO RESPIMAT (5/5 mcg)
2 Geometric mean effective half-life from COPD patients following once daily treatment with 18 mcg Tiotropium HandiHaler® for 14 days
3 Geometric mean (gCV%) AUC over the 24-hour dosing interval from COPD patients following once daily treatment with INSPIOLTO RESPIMAT (5/5 mcg) for 6 weeks
4 Geometric mean (gCV%) values from healthy volunteers administered single dose of 14.4 mcg tiotropium via intravenous infusion
5 Geometric mean (gCV%) terminal half-life determined in healthy volunteers following 2 weeks inhalation of 30 mcg olodaterol
6 Geometric mean (gCV%) values determined following intravenous administration of olodaterol to healthy volunteers
When tiotropium and olodaterol were administered in combination by the inhaled route, the pharmacokinetic parameters for each component were similar to those observed when each active substance was administered separately.
Absorption:
Tiotropium:
Following inhalation by young healthy volunteers, urinary excretion data suggests that approximately 33% of the dose reaches the systemic circulation. Oral solutions of tiotropium have an absolute bioavailability of 2-3%. Food is not expected to influence the absorption of tiotropium. Maximum tiotropium plasma concentrations were observed 5-7 minutes after inhalation. At steady state, peak tiotropium plasma concentrations of 10.5 pg/mL were achieved in COPD patients and decreased rapidly in a multi-compartmental manner. Steady state trough plasma concentrations were 1.60 pg/mL and was reached by day 7 with no accumulation thereafter.
Olodaterol:
Olodaterol is rapidly absorbed, reaching maximum plasma concentrations generally within 10 to 20 minutes following drug inhalation. Olodaterol showed linear pharmacokinetics with a dose-proportional increase of systemic exposure after single inhaled doses of 5 to 70 mcg and multiple once daily inhaled doses of 5 to 20 mcg.
On repeated once daily inhalation steady-state olodaterol plasma concentrations were achieved after 8 days, and the extent of exposure was increased up to 1.8-fold as compared to a single dose.
In healthy volunteers the absolute bioavailability of olodaterol following inhalation was estimated to be approximately 30%, whereas the absolute bioavailability was below 1% when given as an oral solution. Across-study comparisons however suggest somewhat higher systemic exposure in COPD patients than in healthy subjects (~34% higher steady state Cmax, ~23% higher steady state AUC0-1). Maximum olodaterol plasma concentrations generally are reached within 10 to 20 minutes following drug inhalation via RESPIMAT.
Distribution:
Tiotropium:
The drug has a plasma protein binding of 72% and shows a volume of distribution of 32 L/kg. Local concentrations in the lung are not known, but the mode of administration suggests substantially higher concentrations in the lung. Studies in rats have shown that tiotropium does not penetrate the blood-brain barrier to any relevant extent.
Olodaterol:
Olodaterol exhibits multi-compartmental disposition kinetics after inhalation as well as after intravenous administration. The volume of distribution is high (1110 L), suggesting extensive distribution into tissue. In vitro binding of [14C] olodaterol to human plasma proteins is independent of concentration and is approximately 60%.
Metabolism:
Tiotropium:
The extent of biotransformation is small. This is evident from a urinary excretion of approximately 74% of unchanged substance after an intravenous dose to young healthy volunteers. Tiotropium, an ester, is nonenzymatically cleaved to the alcohol N-methylscopine and dithienylglycolic acid, both not binding to muscarinic receptors.
In-vitro experiments with human liver microsomes and human hepatocytes suggest that some further drug (<20% of dose after intravenous administration) is metabolized by cytochrome P450 dependent oxidation and subsequent glutathione conjugation to a variety of Phase II-metabolites. This enzymatic pathway can be inhibited by the CYP450 2D6 (and 3A4) inhibitors, quinidine, ketoconazole and gestodene. Thus CYP450 2D6 and 3A4 are involved in the metabolic pathway that is responsible for the elimination of a smaller part of the dose. Tiotropium bromide even in supra-therapeutic concentrations does not inhibit cytochrome P450 1A1, 1A2, 2B6, 2C9, 2C19, 2D6, 2E1 or 3A in human liver microsomes.
Olodaterol:
Olodaterol is substantially metabolized by direct glucuronidation and by O-demethylation at the methoxy moiety followed by conjugation. Of the six metabolites identified, only the unconjugated demethylation product (SOM 1522) binds to ß2-receptors; this metabolite, however, is not detectable in plasma after chronic inhalation of the recommended therapeutic dose or doses of up to 4-fold higher.
Cytochrome P450 isozymes CYP2C9 and CYP2C8, with negligible contribution of CYP3A4, are involved in the O-demethylation of olodaterol, while uridine diphosphate glycosyl transferase isoforms UGT2B7, UGT1A1, 1A7 and 1A9 were shown to be involved in the formation of olodaterol glucuronides.
Excretion:
Tiotropium:
The effective half-life of tiotropium bromide ranges between 27 to 45 h following inhalation by COPD patients.
Intravenously administered tiotropium bromide to young healthy volunteers is mainly excreted unchanged in urine (74%) with a total clearance of 880 mL/min.
Following 21-day, once daily inhalation of the solution by patients with COPD, 24-hour urinary excretion is 18.6% (0.93 mcg) of the dose, the remainder being mainly non-absorbed drug in gut that is eliminated via the feces.
The renal clearance of tiotropium exceeds the creatinine clearance indicating secretion into the urine. After chronic once daily inhalation by COPD patients, pharmacokinetic steady state was reached by day 7 with no accumulation thereafter.
Olodaterol:
Total clearance of olodaterol in healthy volunteers is 872 mL/min, and renal clearance is 173 mL/min.
The terminal half-life following intravenous administration is 22 hrs. The terminal half-life following inhalation in contrast is about 45 hrs, indicating that the latter is determined by absorption rather than by elimination processes.
Following intravenous administration of [14C]-labelled olodaterol, 42.5% of the radioactive dose was recovered in the urine and 53% was recovered in feces. The amount of unchanged olodaterol recovered in the urine after intravenous administration was 19%. Following oral administration, only 9% of the radioactivity was recovered in urine, while the major portion was recovered in feces (84%). More than 90% of the dose was excreted within 6 and 5 days following intravenous and oral administration, respectively. Following inhalation, excretion of unchanged olodaterol in urine within the dosing interval in healthy volunteers at steady state accounted for 5-7% of the dose.
Clinical Pharmacology
24-hour Bronchodilatory Profile:
The 24-hour lung function profiles of INSPIOLTO RESPIMAT compared to placebo was assessed in patients with moderate to severe COPD (n=219) in a six-week randomized, double-blind, placebo-controlled, cross-over trial. The primary efficacy endpoint was the forced expiratory volume in 1 second (FEV1) AUC0-24 hour response (L) after 6-weeks of treatment.
After 6 weeks of treatment, INSPIOLTO RESPIMAT showed a significantly greater FEV1 response compared to tiotropium 5 mcg, olodaterol 5 mcg and placebo over the full 24 hour dosing interval (Figure 1, Table 4).
Figure 1: FEV1 profile for INSPIOLTO RESPIMAT, tiotropium 5 mcg, olodaterol 5 mcg and placebo over a continuous 24 hour dosing interval after 6 weeks (Trial 1237.20)
Table 4: Difference in FEV1 (L) for INSPIOLTO RESPIMAT compared to tiotropium 5 mcg, olodaterol 5 mcg and placebo over a continuous 24 hour dosing interval after 6 weeks (Trial 1237.20)
| n | 3 hr average | n | 12 hr average | 24 hr average1 | Trough | |
| INSPIOLTO RESPIMAT versus | 138 | 138 | ||||
| Tiotropium 5 mcg | 137 | 0.109 | 135 | 0.119 | 0.110 | 0.079 |
| Olodaterol 5 mcg | 138 | 0.109 | 136 | 0.126 | 0.115 | 0.092 |
| Placebo | 135 | 0.325 | 132 | 0.319 | 0.280 | 0.207 |
pre-treatment baseline FEV1 = 1.30 L
1 primary endpoint
p<0.0001 for all comparisons
More information on lung function from the pivotal studies is found in the CLINICAL TRIALS section under Study results - Lung Function.
Special Populations and Conditions
Pediatrics: The safety and effectiveness of INSPIOLTO RESPIMAT in the pediatric population have not been established.
Geriatrics: Elderly patients can use INSPIOLTO RESPIMAT at the recommended dose.
Tiotropium: As expected for all predominantly renally excreted drugs, advancing age was associated with a decrease of tiotropium renal clearance from 347 mL/min in COPD patients <65 years to 275 mL/min in COPD patients ≥65 years. This did not result in a corresponding increase in AUC0-6,ss or Cmax,ss values.
Gender: Subgroup analyses based on gender did not reveal any interactions that require special consideration.
Race: Comparison of pharmacokinetic data within and across studies with olodaterol revealed a trend for higher systemic exposure in Japanese (approximately 1.7-fold) and other Asians (1.2-fold) than in Caucasians.
Hepatic Insufficiency:
Tiotropium: The effects of hepatic impairment on the pharmacokinetics of tiotropium were not studied. However, impaired liver function is not expected to have any clinically relevant influence on tiotropium pharmacokinetics since tiotropium is predominantly cleared by renal elimination and by non-enzymatic ester cleavage to products that do not bind to muscarinic receptors.
Olodaterol: In subjects with mild and moderate hepatic impairment systemic exposure to olodaterol was not affected. The effect of severe hepatic impairment on systemic exposure to olodaterol was not investigated.
Renal Insufficiency:
Tiotropium: Once daily inhaled administration of tiotropium to steady-state in COPD patients with mild renal impairment (creatinine clearance 60-90 mL/min) resulted in slightly higher AUC0-6,ss (between 6% to 23% higher) and Cmax,ss (between 6% to 17% higher) values compared to patients with normal renal function. Moderate renal impairment (creatinine clearance 30-60 mL/min) resulted in modestly higher AUC0-6,ss (between 54% to 57% higher) and Cmax,ss (between 15% to 31% higher) values compared to COPD patients with normal renal function (creatinine clearance >90 mL/min). In patients with severe renal impairment (creatinine clearance <30 mL/min), a single intravenous administration of tiotropium bromide resulted in approximately 94% higher AUC0-4 and 52% higher Cmax compared to patients with normal renal function.
Olodaterol: In subjects with severe renal impairment (CLCR <30 mL/min) systemic exposure to olodaterol was on average 1.4-fold increased, up to a maximum 2-fold higher compared to healthy volunteers. As well, renal clearance and urinary excretion was lower in renal impaired patients compared to their healthy counterparts. No dose adjustment is required in these patients.
STORAGE AND STABILITY
Store at 15°C–30°C. Do not freeze.
SPECIAL HANDLING INSTRUCTIONS
Prior to first use, the INSPIOLTO RESPIMAT cartridge is inserted into the INSPIOLTO RESPIMAT inhaler and the unit is primed.
When using the unit for the first time, patients are to actuate the inhaler toward the ground until an aerosol (soft mist) cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use. If used every day, no further priming is necessary. If not used for more than 7 days, patients are to actuate the inhaler once to prepare the inhaler for use. If not used for more than 21 days, patients are to actuate the inhaler until an aerosol (soft mist) cloud is visible and then repeat the process three more times to prepare the inhaler for use (see PART III: CONSUMER INFORMATION – PROPER USE OF THIS MEDICATION).
When the labeled number of metered actuations (60 or 28) has been dispensed from the inhaler, the INSPIOLTO RESPIMAT locking mechanism will be engaged and no more actuations can be dispensed.
After insertion of the cartridge into the inhaler, INSPIOLTO RESPIMAT should be discarded at the latest 3 months after first use or when the locking mechanism is engaged (60 or 28 actuations), whichever comes first.
Keep out of reach of children. Do not spray into eyes.
DOSAGE FORMS, COMPOSITION AND PACKAGING
INSPIOLTO RESPIMAT is supplied in a carton containing one INSPIOLTO RESPIMAT cartridge and one INSPIOLTO RESPIMAT inhaler.
The INSPIOLTO RESPIMAT cartridge is an aluminum cylinder with a tamper protection seal on the cap. The drug product, INSPIOLTO RESPIMAT, is composed of an aqueous solution of tiotropium and olodaterol filled into a plastic container crimped into an aluminum cylinder (INSPIOLTO RESPIMAT cartridge) for use with the INSPIOLTO RESPIMAT inhaler.
The INSPIOLTO RESPIMAT inhaler is a propellant free hand-held, pocket-sized, multi-dose, oral inhalation device. The INSPIOLTO RESPIMAT inhaler is a cylindrical-shaped plastic inhalation device with a grey-colored body and a clear base. The clear base is removed to insert the cartridge. The inhaler contains a dose indicator and a locking mechanism that engages after the declared number of doses has been delivered. The light green colored cap on the INSPIOLTO RESPIMAT inhaler is color coded to match the INSPIOLTO RESPIMAT cartridge and the information on the cartridge label indicates that it should be used with the INSPIOLTO RESPIMAT inhaler.
The INSPIOLTO RESPIMAT cartridge when used with the INSPIOLTO RESPIMAT inhaler, is designed to deliver 60 or 28 metered actuations after preparation for use; the equivalent of 30 or 14 days medication when used according to the directions for use (one dose equals two actuations).
Each dose (1 dose equals 2 actuations) from the INSPIOLTO RESPIMAT inhaler delivers 5 mcg tiotropium and 5 mcg olodaterol from the mouthpiece.
As with all inhaled drugs, the actual amount of drug delivered to the lung may depend on patient factors, such as the coordination between the actuation of the inhaler and inspiration through the delivery system. The duration of inspiration should be at least as long as the spray duration (1.5 seconds).
Excipients include purified water, benzalkonium chloride, disodium edetate, and hydrochloric acid.
The INSPIOLTO RESPIMAT cartridge is only intended for use with the INSPIOLTO RESPIMAT inhaler.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
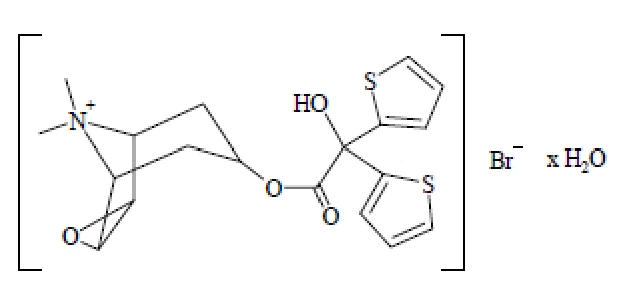
Proper name: tiotropium bromide monohydrate
Chemical name: (1α,2β,4β,5α,7β)-7-[Hydroxydi-2-thienylacetyl)oxy]-9,9dimethyl-3- oxa-9-azoniatricyclo[3.3.1.02,4]nonane bromide monohydrate
Molecular formula and molecular mass: C19H22NO4S2Br • H2O / 490.4 (monohydrate)
C19H22NO4S2Br / 472.4 (anhydrous)
Structural formula:
Physicochemical properties:
| Description: | White or yellowish white powder. It is sparingly soluble in water and soluble in methanol. |
| Polymorphism: | Three crystalline forms are possible, the monohydrate and two anhydrous forms |
| Melting Point: | Between 225oC and 235oC |
| pH (1% aqueous solution): | 5.0 - 5.6 |
| Apparent Partition Coefficient: | log Papp = -2.28 |
Drug Substance
Proper name: olodaterol hydochloride
Chemical name: 2H-1,4-Benzoxazin-3(4H)-one, 6-hydroxy-8-[(1R)-1-hydroxy-2-[[2-(4 methoxyphenyl)-1,1-dimethylethyl]amino]ethyl]-, monohydrochloride
Molecular formula and molecular mass: C21H26N2O5 x HCl / 422.91g/mol (hydrochloride)
C21H27N2O5Cl / 386.45g/mol (free base)
Structural formula:
NH O NH O OH OH CH3 CH3 O CH3 HCl
Physicochemical properties:
| Description: | White to off-white powder |
| Melting Point: | 210 – 220°C (DSC) |
| pH dependent solubility: | Sparingly - slightly soluble (> 20 -1.1 mg/ml) over the entire pH-range. The solubility in water is more than 20 mg/ml at intrinsic pH of 6.2. |
| Solubility in organic solvents: |
|
| Polymorphism: | Polymorphs have not been observed. |
CLINICAL TRIALS
Pivotal Clinical Trials
Trial Design and Patient Demographics
The long-term efficacy and safety of INSPIOLTO RESPIMAT was evaluated in two replicate, 52 week randomized, double-blind, parallel group trials (i.e. trials 1237.5 and 1237.6) comparing INSPIOLTO RESPIMAT with tiotropium 5 mcg and olodaterol 5 mcg (1029 received INSPIOLTO RESPIMAT).
These trials have identical study design including study objectives, efficacy and safety endpoints, inclusion/exclusion criteria, concomitant/restricted medications, and statistical analysis methods. In these trials, the comparator products, tiotropium 5 mcg, olodaterol 5 mcg were administered via the RESPIMAT® inhaler (Table 5).
The primary efficacy endpoints were change from pre-treatment baseline (response) in forced expiratory volume in one second area under the curve (FEV1 AUC0-3h, up to 3 hours post-dose) and trough FEV1 (23-24 hours post dose) after 24 weeks. Other efficacy endpoints that were captured after 24 weeks of treatment included the St. George’s Respiratory Questionnaire (SGRQ) to measure the health-related quality of life and the Mahler Transition Dyspnea Index (TDI) as a measure of dyspnea.
Table 5: Summary of trial design and patient demographics for pivotal clinical trials
| Study # | Trial design | Dosage (oral inhalation) | Study subjects (N) Mean age (Range) Gender (%) | Primary Efficacy Endpoints |
| 1237.5 | 52-week treatment, randomized, double-blind, active-controlled, parallel group | Tio+Olo 2.5/5 mcg Tio+Olo 5/5 mcg Tio 2.5 mcg Tio 5 mcg Olo 5 mcg | N = 2624 64.2 yrs (40-89) M: 73.7% F: 26.3% | FEV1 AUC0-3 and Trough FEV1 at 24 weeks |
| 1237.6 | 52-week treatment, randomized, double-blind, active-controlled, parallel group | Tio+Olo 2.5/5 mcg Tio+Olo 5/5 mcg Tio 2.5 mcg Tio 5 mcg Olo 5 mcg | N = 2538 63.8 yrs (40-97) M: 72.0% F: 28.0% | FEV1 AUC0-3 and Trough FEV1 at 24 weeks |
A total of 5,162 subjects were randomized and treated in 52 week pivotal studies. The subjects had a clinical diagnosis of COPD, were 40 years of age or older, had a history of smoking greater than 10 pack-years, had a relatively stable airway obstruction with a post-salbutamol FEV1 <80% of predicted normal values and a post-bronchodilator FEV1/FVC < 0.7). Concurrent use of long-acting bronchodilators and combinations of inhaled corticosteroids (ICS) and bronchodilators was not allowed. Concurrent use of ICS and oral corticosteroid at a stable dose, and study-provided rescue short acting beta agonist (SABA) was allowed. Subjects with a current diagnosis of asthma, clinically significant uncontrolled disease, a clinically significant laboratory finding, or a diagnosis of paroxysmal tachycardia, unstable cardiac arrhythmia, active tuberculosis, or a history of myocardial infarction or heart failure within the past year were excluded from these trials.
The majority of the 5,162 patients randomized and treated in the 52 week pivotal trials were male (73%), white (71%) or Asian (25%), with a mean age of 64.0 years. Mean post-bronchodilator FEV1 was 1.37 L (GOLD II [50%], GOLD III [39%], and GOLD IV [11%]). Mean β2-agonist responsiveness was 16.6% of baseline (0.171 L). Pulmonary medications allowed as concomitant therapy included inhaled steroids [47%] and xanthine´s [10%].
Study results
Lung Function
In the 52 week pivotal trials, significant improvements were observed in FEV1 AUC0-3h response and trough FEV1 response after 24 weeks (lung function primary endpoints) for INSPIOLTO RESPIMAT compared to tiotropium 5 mcg and olodaterol 5 mcg (Table 6).
Table 6: Difference in FEV1 AUC0-3h and trough FEV1 response for INSPIOLTO RESPIMAT compared to tiotropium 5 mcg, olodaterol 5 mcg after 24 weeks (Trials 1237.5 and 1237.6)
| FEV1 AUC0-3h response | Trough FEV1 response | |||||||||||||||
| Trial 1237.5 | Trial 1237.6 | Trial 1237.5 | Trial 1237.6 | |||||||||||||
| Mean (L) | 95%CI (L) | Mean | 95%CI | Mean | 95%CI | Mean | 95%CI | |||||||||
INSPIOLTO RESPIMAT versus Tiotropium 5 mcg | 0.117 | 0.094, 0.140 | 0.103 | 0.078, 0.127 | 0.071 | 0.047, 0.094 | 0.050 | 0.024, 0.075 | ||||||||
INSPIOLTO RESPIMAT versus Olodaterol 5 mcg | 0.123 | 0.100, 0.146 | 0.132 | 0.108, 0.157 | 0.082 | 0.095, 0.106 | 0.088 | 0.063, 0.113 | ||||||||
pre-treatment baseline FEV1: Trial 1237.5 = 1.16 L; Trial 1237.6 = 1.15 L p≤0.0001 for all comparisons
INSPIOLTO RESPIMAT, administered once daily in the morning, provided clear improvement in lung function within 5 minutes after the first dose compared to tiotropium 5 mcg (mean increase in FEV1 of 0.137 L for INSPIOLTO RESPIMAT vs. 0.058 L for tiotropium 5 mcg [p<0.0001] and 0.125 L for olodaterol 5 mcg [p=0.16]).
The increased bronchodilator effects of INSPIOLTO RESPIMAT compared to tiotropium 5 mcg and olodaterol 5 mcg were maintained throughout the 52 week treatment period (Figures 2 and 3).
Figure 2: Adjusted mean trough FEV1 (L) response over 52 weeks of treatment, trial 1237.5
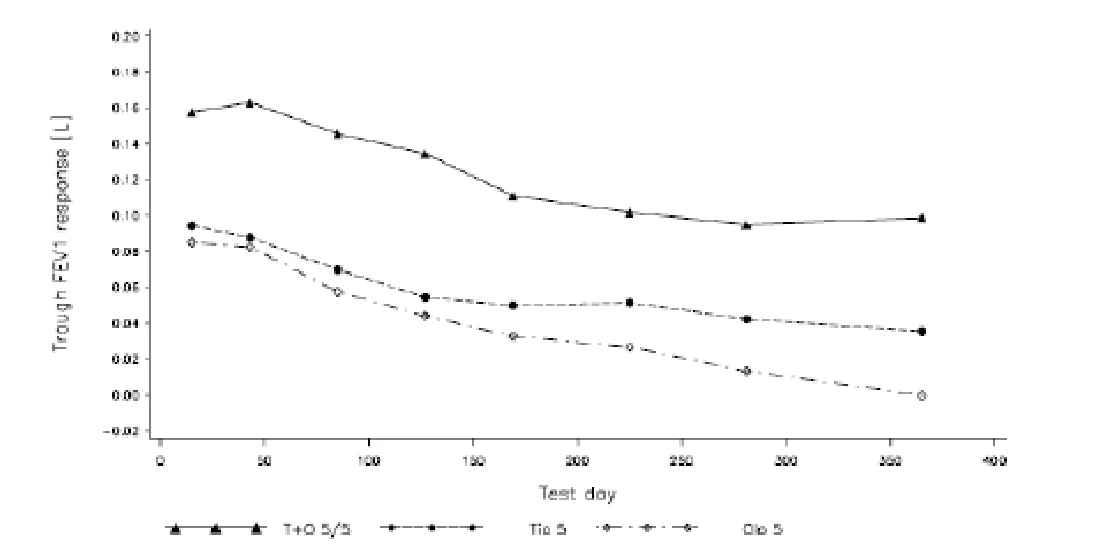
Figure 3: Adjusted mean trough FEV1 (L) response over 52 weeks of treatment, trial 1237.6
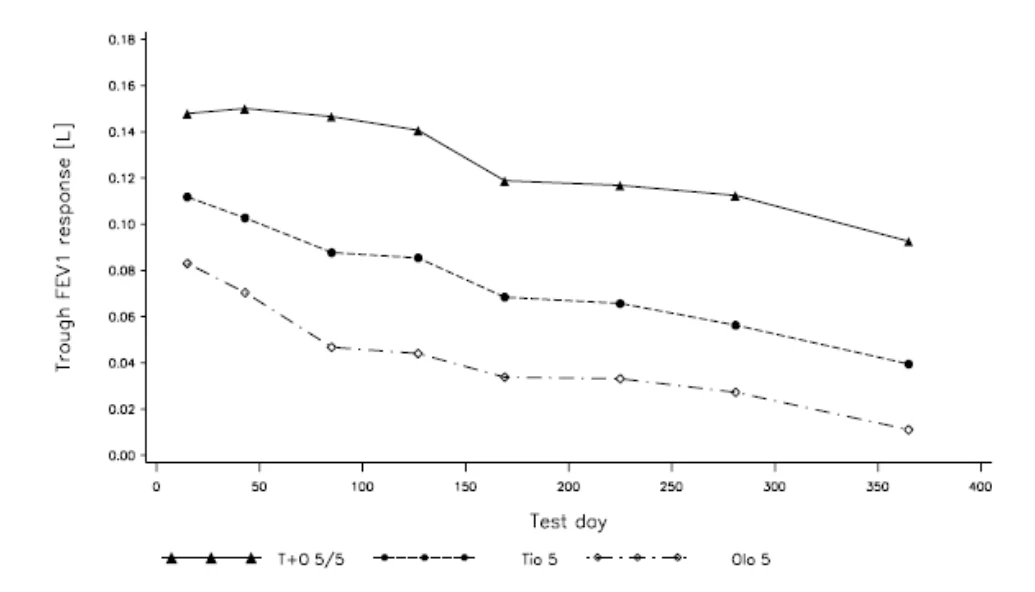
In the sub-set of patients who completed extended lung function measurements up to 12 hrs post-dose, INSPIOLTO RESPIMAT showed a significantly greater FEV1 response compared to tiotropium 5 mcg and olodaterol 5 mcg over the full 24 hour dosing interval (Figure 4). More information on the 24 hour bronchodilatory profile is found in Clinical Pharmacology - 24-hour Bronchodilatory Profile:
Figure 4: FEV1 profile for INSPIOLTO RESPIMAT, tiotropium 5 mcg and olodaterol 5 mcg over a continuous 24 hour dosing interval after 24 weeks (12 hr PFT sub-set from Trials 1237.5 and 1237.6; combined dataset)
Symptom Related Outcomes
Health-related Quality of Life
Health-related quality of life was measured using St. George’s Respiratory Questionnaire (SGRQ) in the pivotal trials. After 24 weeks, INSPIOLTO RESPIMAT improved mean SGRQ total score compared to tiotropium 5 mcg (-1.23 units, 95%CI -2.31, -0.15) and olodaterol 5 mcg (-1.69 units, 95%CI -2.78, -0.61); improvements were seen in all SGRQ domains. More patients treated with INSPIOLTO RESPIMAT had a clinically meaningful improvement in SGRQ total score (MCID, defined as a decrease of at least 4 units from baseline) compared to tiotropium 5 mcg (57.5% vs. 48.7%) and olodaterol 5 mcg (57.5% vs. 44.8%).
Dyspnea
After 24 weeks, INSPIOLTO RESPIMAT demonstrated an improvement in reducing shortness of breath, as measured by mean TDI focal score when compared to tiotropium 5 mcg (0.36 units; 95%CI= 0.09 to 0.62) and olodaterol 5 mcg (0.42 units, 95%CI= 0.16 to 0.68). More patients treated with INSPIOLTO RESPIMAT had a clinically meaningful improvement in TDI focal score (MCID, defined as a value of at least 1 unit) compared to tiotropium 5 mcg (54.9% vs. 50.6%) and olodaterol 5 mcg (54.9% vs. 48.2%).
Rescue Medication Use
Patients treated with INSPIOLTO RESPIMAT used less daytime and night-time rescue salbutamol compared to patients treated with tiotropium 5 mcg and olodaterol 5 mcg.
Supporting Clinical Trials (Exercise Endurance)
Trial Design
The effect of INSPIOLTO RESPIMAT on inspiratory capacity, breathing discomfort and symptom-limited exercise endurance was investigated in two replicate, 6 week randomized, double-blind, placebo-controlled, cross-over trials comparing INSPIOLTO RESPIMAT with tiotropium 5 mcg, olodaterol 5 mcg and placebo during constant work rate cycling (450 received INSPIOLTO RESPIMAT) [Trials 1237.13 and 1237.14], and one 12 week randomized, double-blind, placebo-controlled, parallel group trial comparing INSPIOLTO RESPIMAT with placebo during constant work rate cycling (139 received INSPIOLTO RESPIMAT) and constant speed walking (sub-set of patients) [Trial 1237.15].
The primary efficacy endpoints in trials 1237.13 and 1237.14 were inspiratory capacity (IC) at rest and endurance time (ET) during constant work rate cycle ergometry (CWRCE) to symptom limitation at 75% maximal work capacity (Wcap) after 6 weeks of treatment. The primary efficacy endpoints in trial 1237.15 was endurance time (ET) during constant work rate cycle ergometry (CWRCE) to symptom limitation at 75% maximal work capacity (Wcap) after 12 weeks of treatment while inspiratory capacity (IC) at rest was evaluated as a secondary endpoint.
Study Results
INSPIOLTO RESPIMAT significantly improved inspiratory capacity (IC) compared to tiotropium 5 mcg, olodaterol 5 mcg and placebo after 6 weeks (Trials 1237.13 and 1237.14; Table 7) and compared to placebo after 12 weeks (0.234 L, p<0.0001; Trial 1237.15).
Table 7: Difference in inspiratory capacity at rest (IC) (L) and 95%CI for INSPIOLTO RESPIMAT compared to tiotropium 5 mcg, olodaterol 5 mcg and placebo after 6 weeks (Trials 1237.13 and 1237.14)
| n | Trial 1237.13 1 | n | Trial 1237.142 | |
| INSPIOLTO RESPIMAT versus | 219 | 218 | ||
| Tiotropium 5 mcg | 213 | 0.114 (0.061, 0.167) | 208 | 0.088 (0.039, 0.137) |
| Olodaterol 5 mcg | 214 | 0.119 (0.065, 0.172) | 208 | 0.080 (0.031, 0.129) |
| Placebo | 211 | 0.244 (0.191, 0.298) | 202 | 0.265 (0.215, 0.315) |
1 pre-treatment baseline: 2.53 L, all p values <0.0001
2 pre-treatment baseline: 2.59 L, all p values < 0.0015
In Trials 1237.13 and 1237.14, INSPIOLTO RESPIMAT improved endurance time during constant work rate cycling by 20.9% (p<0.0001) and 13.4% (p<0.0001) respectively, when compared to placebo after 6 weeks of treatment. In Trial 1237.15, INSPIOLTO RESPIMAT improved endurance time during constant work rate cycling by 13.8% (p=0.0209) after 12 weeks compared to placebo.
Supporting Clinical Trials (Symptom Related Outcomes)
In two 12-week, placebo-controlled clinical trials, SGRQ total score at 12 weeks was also evaluated as a measure of health-related quality of life. INSPIOLTO RESPIMAT demonstrated an improvement compared with placebo at week 12 in mean SGRQ total score (primary endpoint) of -4.9 (95%CI: −6.9, −2.9) and -4.6 (95%CI: −6.5, −2.6). In a pooled analysis of the 12-week trials, INSPIOLTO RESPIMAT demonstrated an improvement compared with tiotropium 5 mcg at week 12 in mean SGRQ total score of −2.1 (95%CI: −3.5,−0.7). In the pooled analysis, the proportion of patients with a clinically meaningful decrease in SGRQ total score (defined as a decrease of at least 4 units from baseline) at week 12 was greater for INSPIOLTO RESPIMAT (52%) compared with tiotropium 5 mcg (41%) and placebo (32%).
Supporting Clinical Trials (Exacerbations)
Tiotropium 5mcg has previously demonstrated a statistically significant reduction in risk of a COPD exacerbation compared to placebo.
In a one-year, randomized, double-blind, active-controlled parallel group clinical trial, INSPIOLTO RESPIMAT was compared with tiotropium 5 mcg on COPD exacerbations. Exacerbations were defined as “a complex of lower respiratory events/symptoms (increase or new onset) related to the underlying COPD, with duration of three days or more, requiring a prescription of antibiotics and/or systemic steroids and/or hospitalization.” Enrolled patients (3939 patients receiving INSPIOLTO RESPIMAT and 3941 patients receiving tiotropium 5 mcg) had a history of COPD exacerbation in the previous 12 months. All respiratory medications except anticholinergics, long-acting beta-agonists and combinations thereof were allowed as concomitant treatment, i.e. rapidly acting beta-agonists, inhaled corticosteroids and xanthines. The primary efficacy endpoint was the annualized rate of moderate to severe COPD exacerbations. The majority of patients were male (71%) and Caucasian (79%). The mean age was 66 years, and mean post-bronchodilator FEV1 percent predicted was 45%. INSPIOLTO RESPIMAT treatment did not demonstrate superiority to tiotropium 5 mcg for the primary endpoint, the annualized rate of moderate to severe COPD exacerbations, with a rate ratio of 0.93 (99% CI, 0.85-1.02, p=0.0498). The study did not reach the pre-specified significance level of p<0.01.
DETAILED PHARMACOLOGY
Animal Pharmacology
Pharmacological effects seen with tiotropium or olodaterol in nonclinical studies were those typically associated with either muscarinic antagonist or beta2-agonists.
Human Pharmacology
Please refer to ACTION AND CLINICAL PHARMACOLOGY
TOXICOLOGY
Toxicological effects seen with tiotropium or olodaterol in nonclinical studies were those typically associated with either muscarinic antagonist or beta2-agonists and/or local irritancy.
Tiotropium:
Acute Toxicity
The acute inhalation and oral toxicity in mice, rats and dogs was low and independent of the formulation type used (aqueous aerosol, lactose powder). Non-lethal dosages produced clinical signs characteristic of the pharmacodynamic activity of tiotropium (mydriasis, dry mouth and nose) as well as non-specific signs of toxicity (dyspnea, tremor, ataxia, convulsions, loss of motility and body weight). In mice, deaths occurred at 131 mg/kg tiotropium when administered as an aqueous aerosol through nose only exposure (the LD50-value could not be established). No lethal dosage was achieved by the inhalation of either formulation in rats (LD50 > 334.5 mg/kg) or dogs (LD50 > 3.6 and > 0.7 mg/kg). Necropsy of decedents revealed pulmonary emphysema and/or congestion of liver and kidneys. No gross lesions were detected among survivors. The oral LD50 for mice and rats are 219,099 and 1,279,279 times respectively the maximum recommended human dose on a mg/m2 basis.
Chronic Toxicity
The repeated-dose toxicity was investigated by inhalation of tiotropium by rats and Beagle dogs for 13 and 52 weeks, by intravenous injection over 4 weeks, and by oral gavage for 13 weeks. In rats and dogs, most in-life and morphological changes were directly or indirectly attributable to the anticholinergic activity of the compound. These changes included mydriasis, increased heart rate, and dry mucous membranes due to lowered secretory activity of the lacrimal glands as well as of the glands of the digestive and upper respiratory tract. The anticholinergic activity of the compound most probably also accounted for distension of the large bowel, and for the species-specific deposition of proteinaceous material in the urinary bladder of male rats. Subsequently, secondary indirect changes developed, such as rhinitis and keratoconjunctivitis sicca, as well as decreased food consumption, body weight gain, liver lipids, serum glucose and triglycerides. Thymic involution and changes of the Harderian gland including chromodacryorrhea were regarded as non-specific responses to stress.
Even low dosages induced signs characteristic of the anticholinergic activity of tiotropium; therefore, a no observed toxic event level (NOTEL) could only be established in a limited number of studies. In the rat, the inhalation NOTEL was < 0.013 mg/kg and the inhalation NOTEL in the dog was > 0.010 mg/kg. The few changes that were perhaps unexpected include urogenital tract changes and cataracts in rats. The urogenital changes are nevertheless considered as sequelae to pharmacological effects and as such are part of a syndrome that includes the prostate. In view of the species-specificity of the syndrome and its harmless nature, it is unlikely to have any influence on human safety assessment. Similarly, although the precise mechanism remains unknown, cataract formation appears to be specific to Wistar rats and to the mode of administration. As the method of administration to the patient avoids direct eye exposure to tiotropium, any risk to patients is negligible.
Reproductive Toxicity
The effects of tiotropium (Ba 679 BR) administered via inhalation on the fertility and early embryonal development (Segment I), and on the peri- and postnatal development (Segment III) were assessed in rats, and those on the embryo-fetal development (Segment II) were investigated in rats and rabbits. Dose dependent paternal and maternal toxicity was observed. Embryo-fetal toxicity, considered secondary to maternal toxicity, was observed at high doses in rats and rabbits. There was no impairment of reproductive function of the F0 generation and no effect on the postnatal development of the F1 generation. The incidence of variations was increased at dose levels above 0.01 mg/kg but they were of the types encountered in the historical controls. No teratogenicity was noted.
The No Observed Toxic Effect Level (NOTEL) for maternal/paternal toxicity in the rat and rabbit was < 0.01 mg/kg Ba 679 BR and for developmental toxicity 0.01 mg/kg in all three segments when administered by inhalation.
In a general reproduction and fertility study in rats, there was no indication of any adverse effect on fertility or mating performance of either treated parents or their offspring at clinically relevant dosages.
Carcinogenicity and Mutagenicity
Inhalation carcinogenicity studies in mice and rats have revealed no carcinogenic potential at target tiotropium doses up to 2.54, 180 and 75 mcg/kg/day (male mice, female mice and rats, respectively). These doses correspond to about 0.45, 92 and 27 times the maximum recommended human dose (MRHD) on a mg/m2 basis.
Results of various mutagenicity studies (Ames test and E coli bacterial gene mutation test, gene mutation test in V79 Chinese hamster cells, in vitro cytogenetic study with human lymphocytes, in vitro unscheduled DNA-synthesis test, and in vivo micronucleus test) were negative.
Olodaterol:
Acute Toxicity
Acute toxicity after single-dose inhalation, intravenous and oral administration in mice and rats, was low. Single oral administrations of olodaterol were well tolerated in mice and rats up to 1000 mg/kg and 316 mg/kg, respectively. The single-dose safety pharmacology studies showed the expected effects of a beta2-adrenergic agonist including decreased blood pressure, and increased heart rate and force of contraction.
Repeat-dose Toxicity
The effects in the inhalation repeat-dose studies in mice, rats and dogs were mainly related to beta2-adrenergic properties of olodaterol including increased body weight and muscle mass and food consumption (rodents). Reduced epididymides and testes weights and increased ovary and uterus weights as well as increased heart weight were commonly observed in rodents. The effects of olodaterol in the toxicity studies in dogs were mainly an increase in heart rate, changes in glycogen distribution in the liver and papillary muscle necrosis as well as an increased body weight and elevated creatine kinase and plasma creatinine levels related to the beta2-adrenergic properties of olodaterol.QTc prolongation was observed in dogs only after oral administration of olodaterol. Irritancy of the upper respiratory tract in mice and rats consisting of epithelial changes of the nasal cavity and larynx and necrosis of the U shaped cartilage in the larynx were observed at all doses including vehicle and therefore may be attributed to the formulation. All these findings were observed only at exposures in excess of the human exposure at 5 mcg olodaterol. The clinical significance of these is likely of little relevance, yet they do remain unclear.
Table 8: Sub-chronic and chronic toxicology (pivotal studies, longest treatment duration only)
| Study Type | Species | Route | Doses [mcg/kg/day] | Findings |
|---|---|---|---|---|
| 13-week | CD1 Mouse | Inhalation | 63, 211, 900 3258 | Findings at all doses comprised excess salivation, increased body weight, food consumption, K+values, decreased triglycerides values, increased weights of lung, spleen and heart. At ≥211 mcg/kg increased ovarian and uterus weight, squamous metaplasia of the larynx. At ≥900 mcg/kg muscle mass was mildly increased. At 3258 mcg/kg thickened uterus and myometrium and increase nos of corpora lutea and cystic glands in the endometrium. In all groups, including controls, transitional cell hyperplasia of the laryngeal epithelium. NOAEL = 63 mcg/kg/day, not considering pharmacodynamic effects |
| 26-week | Wistar Rat | Inhalation | 49, 200, 3400 | Findings at all doses comprised increased body weight, food consumption, increased skeletal muscle mass and slightly elevated liver parameters, decreased white adipose tissue and degeneration of laryngeal cartilage. At 200 mcg/kg decreased liver glycogen, squamous metaplasia in the larynx and foam cells in the lungs. In addition at 3400 mcg/kg irritation of the respiratory tract, squamous metaplasia in the nasal cavities, larynx & tracheal bifurcation, hemorrhages in corpora lutea, distension of uterus horns, decreased tested weights. All findings were reversible after recovery. NOAEL = 200 mcg/kg/day, not considering pharmacodynamic effects |
| Study Type | Species | Route | Doses [mcg/kg/day] | Findings |
|---|---|---|---|---|
| 52-week | Beagle Dog | Inhalation | 15, 60, 330 | Findings at all doses comprised increase heart force, heart rate with mitigation as the study progressed, dry mouth mucosa, increased body weight CK and plasma creatinine values, decreased prostate weight. At 60 mcg/kg ventricular arrhythmias, increased QTf, cTnI and fibrotic foci in the myocardium of left papillary muscles, change of the glycogen distribution and content in liver, glandular atrophy of the prostate were observed. In addition at 330 mcg/kg increases in blood pressure and glandular atrophy of the prostate. NOAEL = 15 mcg/kg/day, not considering pharmacodynamic effects |
Reproductive Toxicity
In rats, no teratogenic effects occurred after inhalation at doses 1054 mcg/kg/day (> 2600 times the human exposure (AUC(0-24h)) at the dose of 5 mcg). In pregnant NZW rabbits, an inhalation dose of 2489 mcg/kg/day (approximately 7130 times the human exposure at 5 mcg based on AUC(0-24h)) of olodaterol exhibited fetal toxicity characteristically resulting from beta-adrenoceptor stimulation; these included patchy ossifications, short/bent bones, partially open eye, cleft palate, cardiovascular abnormalities. No significant effects occurred at an inhalation dose of 974 mcg/kg (approximately 1353 times the 5 mcg dose based on AUC(0-24h)).
No impairment of male or female fertility or early embryonic development was seen in the rat up to inhalation doses of 3068 mcg/kg (approximately 2332 times the 5 mcg dose based on AUC(0-24h)).
No effects were observed on mating, fertility or bearing of live implants to Day 14/15/16 of gestation in the F1 animals in the rat up to inhalation doses of 3665 mcg/kg/day (approximately 2332 times the 5 mcg dose based on AUC(0-24h)).
Table 9: Reproductive Toxicology (pivotal studies)
| Study Type | Species | Route | Doses [mcg/kg/day] | Findings |
|---|---|---|---|---|
| Fertility, reproductive performance and early embryonic development | SD Rat | Inhalation | 58, 192, 3068 | Findings at all doses comprised excessive salivation, reddened skin, increased body weight, food consumption, decreased weights of testes and epididymides. At 3068 mcg/kg: subdued behavior. NOAEL paternal / maternal: = 58 mcg/kg/day, NOAEL fertility / embryonic development / mating: = 3068 mcg/kg/day |
| Study Type | Species | Route | Doses [mcg/kg/day] | Findings |
|---|---|---|---|---|
| Embryo-fetal development | SD Rat | Inhalation | 64, 222, 1054 | Maternal findings at all doses were increased body weight, food consumption. Embryo-fetal findings comprised increased body weight at all doses. NOAEL maternal & embryo-fetal = 1054 mcg/kg/day |
| Embryo-fetal development | NZW Rabbit | Inhalation | 289, 974, 2489 | Maternal findings at all doses were increased body weight. Embryo-fetal findings at 2489 mcg/kg comprised thickened ribs/distorted rib cage, short/bent scapula/humerus/ radius/ulna/femur/ tibia/fibula and/or limb flexure combined, partially open eye and/or cleft palate, unossified areas/patchy ossification of the cranial bones/ribs/long bones; cardiovascular abnormalities. NOAEL maternal = 2489 mcg/kg/day, NOAEL embryo-fetal = 974 mcg/kg/day |
| Pre- and postnatal development, including maternal function | SD Rat | Inhalation | 58, 297, 3665 | Maternal findings at all doses comprised increased body weight gain, salivation NOAEL F0 & F1 generation: = 3665 mcg/kg/day |
Genotoxicity
In the in vivo rat bone marrow micronucleus assay after inhalation exposure (up to approximately 1092 times the 5 mcg dose based on AUC(0-24h)) and the in vitro (Ames test, mouse lymphoma assay) mutagenicity assays, olodaterol was free of any genotoxic potential up to very high dose levels. An increased frequency of micronuclei was observed in rats after i.v. exposure at doses of at least 5500-times the 5 mcg dose based on AUC(0-24h) may be related to drug enhanced (compensatory) erythropoiesis.
Carcinogenicity
Lifetime treatment of rats induced class- and rodent-specific leiomyomas of the mesovarium at exposures approximately 198-fold and 18-fold the exposure at the dose of 5 mcg based on AUC(0-24h).. Lifetime treatment of mice induced class- and rodent-specific smooth muscle tumours (leiomyomas, leiomyosarcomas) of the uterus and incidences of sex cord stromal focal hyperplasia and luteal focal hyperplasia in the ovary at exposures approximately 42- to 318-fold the exposure at the dose of 5 mcg based on AUC(0-24h). Increases in leiomyomas and leiomyosarcomas of the female rodent reproductive tract have been similarly demonstrated with other β2-adrenergic agonist drugs. The relevance of these findings to human use is unknown.
Table 10: Carcinogenicity
| Study Type | Species | Route | Doses [mcg/kg/day] | Findings |
| Carcinogenicity | Mouse CD1 | Inhalation | 26, 77, 255 | Findings at all doses comprised increased body weight, food consumption, muscle mass At doses ≥77 mcg/kg/day increased incidences of leiomyomas and leiomyosarcomas of the uterus, sex cord stromal focal hyperplasia and luteal focal hyperplasia of the ovary. No tumor findings were observed in male mice at doses up to 255 mcg/kg/day. |
| Carcinogenicity | Wistar Rat | Inhalation | 26, 76, 270 | Findings at all doses comprised increased body weight, food consumption, muscle mass. At doses ≥26 mcg/kg/day increased incidences of leiomyomas of the mesovarium |
Tiotropium + Olodaterol
Single-dose toxicity
For the combination tiotropium + olodaterol single-dose toxicity studies after inhalation administration have been performed for three dose ratios in mice and rats, revealing a low acute toxicity. In mice, the approximate lethal doses (ALD) were 34.8+36.6 mg/kg for tiotropium + olodaterol in the ratio 1:1. In rats, no deaths occurred, therefore the ALDs were >17.9+18.8 mg/kg for tiotropium/olodaterol in the ratio 1:1.
Repeat-dose toxicity
Inhalation repeat-dose toxicity studies for the combination tiotropium + olodaterol were performed in rats (4 weeks) and dogs (up to 13 weeks) at different dose ratios. In the 13-week studies in dogs, body weight development, clinical signs, changes of the cardiovascular system and of respective enzyme activities as well as the macroscopical and microscopical pathology were characteristic β2-agonistic and anticholinergic effects. In the 13-week toxicity studies with the dose ratio 1:1 for tiotropium/olodaterol, the no observed adverse effect levels (NOAEL) were 14+16 mcg/kg/day.
Reproduction toxicity
No reproduction toxicity studies for the combination were performed.
Genotoxicity
In vitro mutagenicity for tiotropium or olodaterol alone, did not show any genotoxic potential. In the in vivo rat bone marrow micronucleus assay, after inhalation at dose levels of up to 2266+2174 mcg/kg/day tiotropium + olodaterol for 4 weeks (dose ratio 1:1), the combination was free of genotoxic potential.
Carcinogenicity
No carcinogenicity studies for the combination were performed.
REFERENCES
- 1. Current Spiriva Respimat Product Monograph.
- 2. Current Striverdi Respimat Product Monograph.