


Product Monograph - Trelegy Ellipta
RECENT MAJOR LABEL CHANGES
Not applicable.
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .......................................................................................... 2
TABLE OF CONTENTS ............................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION .................................................................... 4
1 INDICATIONS ............................................................................................................. 4
1.1 Pediatrics .................................................................................................................. 4
1.2 Geriatrics .................................................................................................................. 4
2 CONTRAINDICATIONS ................................................................................................ 4
4 DOSAGE AND ADMINISTRATION ................................................................................ 5
4.1 Dosing Considerations ............................................................................................. 5
4.2 Recommended Dose and Dosage Adjustment ........................................................ 6
4.4 Administration ......................................................................................................... 7
4.5 Missed Dose ............................................................................................................. 7
5 OVERDOSAGE ............................................................................................................ 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 8
7 WARNINGS AND PRECAUTIONS ................................................................................. 9
7.1 Special Populations ................................................................................................ 16
7.1.1 Pregnant Women ............................................................................................. 16
7.1.2 Breast-feeding .................................................................................................. 16
7.1.3 Pediatrics .......................................................................................................... 17
7.1.4 Geriatrics .......................................................................................................... 17
8 ADVERSE REACTIONS............................................................................................... 17
8.1 Adverse Reaction Overview ................................................................................... 17
8.2 Clinical Trial Adverse Reactions ............................................................................. 17
8.3 Less Common Clinical Trial Adverse Reactions ...................................................... 21
8.5 Post-Market Adverse Reactions ............................................................................. 22
9 DRUG INTERACTIONS .............................................................................................. 22
9.2 Drug Interactions Overview ................................................................................... 22
9.4 Drug-Drug Interactions .......................................................................................... 23
9.5 Drug-Food Interactions .......................................................................................... 25
9.6 Drug-Herb Interactions .......................................................................................... 25
9.7 Drug-Laboratory Test Interactions......................................................................... 25
10 CLINICAL PHARMACOLOGY ...................................................................................... 26
10.1 Mechanism of Action ....................................................................................... 26
10.2 Pharmacodynamics .......................................................................................... 27
10.3 Pharmacokinetics ............................................................................................. 31
11 STORAGE, STABILITY AND DISPOSAL ........................................................................ 36
12 SPECIAL HANDLING INSTRUCTIONS .......................................................................... 36
PART II: SCIENTIFIC INFORMATION ..................................................................................... 38
13 PHARMACEUTICAL INFORMATION .......................................................................... 38
14 CLINICAL TRIALS ...................................................................................................... 39
14.1 Clinical Trials by Indication .............................................................................. 39
COPD ................................................................................................................................ 39
Asthma ............................................................................................................................. 45
15 MICROBIOLOGY ...................................................................................................... 50
16 NON-CLINICAL TOXICOLOGY .................................................................................... 50
17 SUPPORTING PRODUCT MONOGRAPHS ................................................................... 51
PATIENT MEDICATION INFORMATION ................................................................................ 52
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TRELEGY ELLIPTA (fluticasone furoate/umeclidinium/vilanterol) is a combination of an inhaled corticosteroid (ICS), long-acting muscarinic antagonist (LAMA), and a long-acting beta2-adrenergic agonist (LABA).
COPD
TRELEGY ELLIPTA 100/62.5/25 mcg is indicated in adult patients who are not adequately treated by a combination of an ICS/LABA or a combination of a LAMA/LABA:
- for the long-term, once daily, maintenance treatment of airflow obstruction in patients with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and/or emphysema (see 14 CLINICAL TRIALS).
- to reduce exacerbations of COPD in patients with a history of exacerbations (see 14 CLINICAL TRIALS).
TRELEGY ELLIPTA is not indicated for the relief of acute bronchospasm (see 7 WARNINGS AND PRECAUTIONS, General).
Asthma
TRELEGY ELLIPTA 100/62.5/25 mcg and 200/62.5/25 mcg are indicated for the long-term, once-daily, maintenance treatment of asthma in patients aged 18 years and older who are not adequately controlled with a maintenance combination of a medium or high dose of an ICS and a LABA (see 14 CLINICAL TRIALS).
TRELEGY ELLIPTA is not indicated for the relief of acute bronchospasm (see 7 WARNINGS AND PRECAUTIONS, General).
1.1 Pediatrics
Pediatrics (<18 years of age): The safety and efficacy of TRELEGY ELLIPTA in pediatric patients below 18 years of age have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): No dosage adjustment is required in patients 65 years of age and older.
2 CONTRAINDICATIONS
TRELEGY ELLIPTA is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
TRELEGY ELLIPTA is contraindicated in patients with severe hypersensitivity to milk proteins (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
COPD and Asthma
- As with other inhaled drugs containing beta2-adrenergic agents, TRELEGY ELLIPTA should not be used more often than recommended, at higher doses than recommended, or in conjunction with other medicines containing LABA or LAMA, as an overdose may result.
- When beginning treatment with TRELEGY ELLIPTA, patients who have been taking rapid onset, short duration, inhaled beta2-agonists on a regular basis should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief if they develop acute respiratory symptoms while taking TRELEGY ELLIPTA.
- TRELEGY ELLIPTA should not be used to treat acute symptoms of COPD or asthma. Patients should be prescribed a rapid onset, short duration inhaled bronchodilator (e.g., salbutamol) to relieve acute symptoms such as shortness of breath and advised to have this available for use at all times.
- Patients should be made aware that for optimum benefit, TRELEGY ELLIPTA must be used regularly, even when asymptomatic.
COPD
- Counselling by healthcare professionals on smoking cessation should be the first step in treating patients with COPD who smoke, independent of the clinical presentation i.e., chronic bronchitis (with or without airflow limitation) or emphysema. Cessation of smoking produces dramatic symptomatic benefits and has been shown to confer a survival advantage.
Asthma
- Patients with asthma should be regularly reassessed by a healthcare professional so that the strength of TRELEGY ELLIPTA they are receiving remains optimal and is only changed on medical advice.
- Healthcare professionals should only prescribe TRELEGY ELLIPTA for patients not adequately controlled on long-term asthma control treatment with a medium or high dose inhaled corticosteroid and a LABA.
- The starting dose of TRELEGY ELLIPTA should be based on the patients' previous asthma therapy including the inhaled corticosteroid dosage.
- If a previously effective dose of TRELEGY ELLIPTA fails to provide adequate control of asthma symptoms, patients should seek medical advice as this indicates worsening of their underlying condition.
4.2 Recommended Dose and Dosage Adjustment
The recommended dose of TRELEGY ELLIPTA in adults 18 years of age and older is:
| COPD | Asthma | |
| TRELEGY ELLIPTA 100/62.5/25 mcg | One inhalation once daily | One inhalation once daily |
| TRELEGY ELLIPTA 200/62.5/25 mcg | Not indicated | One inhalation once daily |
COPD
The recommended and maximum dose is one inhalation of TRELEGY ELLIPTA 100/62.5/25 mcg once daily.
TRELEGY ELLIPTA 200/62.5/25 mcg is not indicated for the treatment of COPD.
Asthma
The recommended dose is one inhalation of TRELEGY ELLIPTA 100/62.5/25 mcg or 200/62.5/25 mcg once daily.
A starting dose of TRELEGY ELLIPTA 100/62.5/25 mcg should be considered for patients who require a low to mid dose of inhaled corticosteroid in combination with a LAMA and a LABA.
TRELEGY ELLIPTA 200/62.5/25 mcg should be considered for patients who require a higher dose of inhaled corticosteroid in combination with a LAMA and a LABA.
For patients who do not respond adequately to TRELEGY ELLIPTA 100/62.5/25 mcg once daily, consider increasing the dose to 200/62.5/25 mcg once daily, which may provide improvement in asthma control.
The maximum recommended dose is 1 inhalation of TRELEGY ELLIPTA 200/62.5/25 mcg once daily.
Geriatrics
No dosage adjustment is required in patients 65 years of age and older (see 10.3 Pharmacokinetics, Special Populations and Conditions, Geriatrics).
Pediatrics
TRELEGY ELLIPTA should not be used in patients under 18 years of age.
Hepatic Insufficiency
For patients with moderate or severe hepatic impairment, the maximum dose is 100/62.5/25 mcg. Caution should be exercised when dosing patients with hepatic impairment who may be more at risk of systemic adverse reactions associated with corticosteroids. Patients should be monitored for corticosteroid-related side effects (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency).
Renal Insufficiency
No dose adjustment is required for patients with renal impairment (see 10.3 Pharmacokinetics, Special Populations and Conditions, Renal Insufficiency).
4.4 Administration
TRELEGY ELLIPTA is for oral inhalation only.
TRELEGY ELLIPTA should be administered as a single dose once-daily at the same time of the day each day. After inhalation, patients should rinse their mouth with water (without swallowing).
Do not use TRELEGY ELLIPTA more than once every 24 hours.
4.5 Missed Dose
If a dose is missed, the patient should be instructed to take the next dose when it is due. The patient should be instructed not to take an extra dose.
5 OVERDOSAGE
No data from clinical studies are available regarding overdose of TRELEGY ELLIPTA.
An overdose of TRELEGY ELLIPTA may produce signs, symptoms or adverse effects associated with the individual components’ pharmacological actions as described below.
In the event of drug overdose, discontinue TRELEGY ELLIPTA and initiate appropriate symptomatic and/or supportive therapy. The judicious use of a cardioselective beta receptor blocker may be considered, bearing in mind that such medicine can produce bronchospasm.
Cardiac monitoring including electrocardiogram monitoring is recommended in cases of overdosage.
Fluticasone Furoate
Chronic overdosage (use at excessive doses for prolonged periods) may result in signs/symptoms of hypercorticism (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
The potential for acute toxic corticosteroid effects following overdosage with TRELEGY ELLIPTA is low. Because of low systemic bioavailability (15.2%) and an absence of acute drug related systemic findings in clinical trials, overdosage of fluticasone furoate is unlikely to require any treatment other than observation.
Single- and repeat-dose trials of fluticasone furoate at doses of 50 to 4,000 mcg have shown fluticasone furoate to be well tolerated. Decreases in mean serum cortisol were observed at dosages of 500 mcg or higher given once daily for 14 days.
Umeclidinium
An overdose of umeclidinium will likely produce signs and symptoms consistent with the known inhaled muscarinic antagonist adverse effects (e.g., dry mouth, visual accommodation disturbances and tachycardia). However, there were no systemic anticholinergic adverse effects following a once-daily inhaled dose of up to 1,000 mcg umeclidinium (16 times the maximum recommended daily dose) for 14 days in subjects with COPD.
Vilanterol
The expected signs and symptoms with overdosage of vilanterol are those typical of excessive beta-adrenergic stimulation (e.g., angina, hypertension or hypotension, tachycardia with rates up to 200 beats/min, arrhythmias, QTc prolongation, nervousness, headache, tremor, seizures, muscle cramps, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, insomnia, hyperglycemia, hypokalemia, metabolic acidosis). As with all inhaled sympathomimetic medicines, cardiac arrest and even death may be associated with an overdose of vilanterol.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 Dosage Forms, Strengths, Composition and Packaging
* See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS sections.
TRELEGY ELLIPTA consists of an inhaler device with a plastic light grey body, a beige mouthpiece cover and a dose counter. The inhaler device encompasses two double foil blister strips both having either 14 or 30 blisters each. On one strip, each blister contains a white dry powder mixture of micronized fluticasone furoate (100 or 200 mcg) and lactose monohydrate. On the other strip, each blister contains a white dry powder mixture of micronized umeclidinium bromide (74.2 mcg, equivalent to 62.5 mcg of umeclidinium), micronized vilanterol trifenatate (40 mcg equivalent to 25 mcg of vilanterol), lactose monohydrate and magnesium stearate. The lactose monohydrate contains milk proteins. After the inhaler is activated, the powder within both blisters is exposed and ready for dispersion into the airstream created by the patient inhaling through the mouthpiece.
Comparative in vitro data for drug delivery and aerodynamic particle size distribution of the delivered drugs fluticasone furoate (100 mcg), umeclidinium (62.5 mcg), and vilanterol (25 mcg) demonstrated that there were no pharmaceutical interactions and each drug was delivered in a comparable manner whether administered via a single ELLIPTA inhaler or from separate inhalers.
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral inhalation | Dry powder for oral inhalation 100 mcg or 200 mcg fluticasone furoate 62.5 mcg umeclidinium (as bromide) 25 mcg vilanterol (as trifenatate) | Lactose monohydrate* (which contains milk protein) and magnesium stearate |
TRELEGY ELLIPTA 100/62.5/25 mcg: Each single inhalation dispenses 100 mcg of fluticasone furoate, 62.5 mcg of umeclidinium (as bromide) and 25 mcg of vilanterol (as trifenatate). Each single inhalation provides a delivered dose (the dose leaving the mouthpiece) of 92 mcg of fluticasone furoate, 55 mcg of umeclidinium (as bromide) and 22 mcg of vilanterol (as trifenatate), when tested under standardized in vitro conditions at a flow rate of 60 L/min for 4 seconds.
TRELEGY ELLIPTA 200/62.5/25 mcg: Each single inhalation dispenses 200 mcg of fluticasone furoate, 62.5 mcg of umeclidinium (as bromide) and 25 mcg of vilanterol (as trifenatate). Each single inhalation provides a delivered dose (the dose leaving the mouthpiece) of 184 mcg of fluticasone furoate, 55 mcg of umeclidinium (as bromide) and 22 mcg of vilanterol (as trifenatate), when tested under standardized in vitro conditions at a flow rate of 60 L/min for 4 seconds.
In adult subjects with severe asthma, mean peak inspiratory flow through the ELLIPTA inhaler was 96.6 L/min (range: 72.4 to 124.6 L/min).
In adult subjects with very severe COPD (FEV1/FVC [forced vital capacity] <70% and FEV1 <30% predicted), mean peak inspiratory flow through the ELLIPTA inhaler was 65.8 L/min (range: 43.5 to 94.1 L/min). The actual amount of drug delivered to the lung will depend on patient factors, such as inspiratory flow profile.
7 WARNINGS AND PRECAUTIONS
General
Serious Asthma-Related Events – Hospitalizations, Intubations, Death: Use of LABA as monotherapy (without ICS) for asthma is associated with an increased risk of asthma-related death (see Salmeterol Multicenter Asthma Research Trial (SMART)). Available data from controlled clinical trials also suggest that use of LABA as monotherapy increases the risk of asthma-related hospitalization in pediatric and adolescent patients. These findings are considered a class effect of LABA monotherapy. When LABA are used in fixed-dose combination with ICS, data from large clinical trials do not show a significant increase in the risk of serious asthma-related events (hospitalizations, intubations, death) compared with ICS alone (see Serious Asthma-Related Events with Inhaled Corticosteroid/Long-acting Beta2-adrenergic Agonist Combination Products).
Serious Asthma-Related Events with Inhaled Corticosteroid/Long-acting Beta2-adrenergic Agonist Combination Products
Four (4) large, 26-week, randomized, double-blind, active-controlled clinical safety trials were conducted to evaluate the risk of serious asthma-related events when LABA were used in fixed-dose combination with ICS compared with ICS alone in subjects with asthma. Three (3) trials included adult and adolescent subjects aged 12 years and older: 1 trial compared budesonide/formoterol with budesonide, 1 trial compared fluticasone propionate/salmeterol with fluticasone propionate, and 1 trial compared mometasone furoate/formoterol with mometasone furoate. The fourth trial included pediatric subjects aged 4 to 11 years and compared fluticasone propionate/salmeterol with fluticasone propionate. No safety study was conducted with TRELEGY ELLIPTA. The primary safety endpoint for all 4 trials was serious asthma-related events (hospitalizations, intubations, death). A single, blinded, independent, joint adjudication committee determined whether events were asthma related.
The 3 adult and adolescent trials were designed to rule out a 2.0-fold increase in relative risk for ICS/LABA compared with ICS. Each individual trial met its pre-specified objective and demonstrated non-inferiority of ICS/LABA to ICS alone. A meta-analysis of the 3 adult and adolescent trials did not show a significant increase in risk of a serious asthma-related event with ICS/LABA fixed-dose combination compared with ICS alone. These trials were not designed to rule out all risk for serious asthma-related events with ICS/LABA compared with ICS.
Table 2 Meta-analysis of Serious Asthma-Related Events in Subjects with Asthma Aged 12 Years and Older
| ICS/LABA (n=17,537)a | ICS (n=17,552)a | ICS/LABA vs. ICS Hazard Ratio (95% CI)b | |
|---|---|---|---|
Serious asthma-related eventc Asthma-related death Asthma-related intubation (endotracheal) Asthma-related hospitalization (≥24-hour stay) | 116 2 1 115 | 105 0 2 105 | 1.10 (0.85, 1.44) |
ICS = Inhaled Corticosteroid; LABA = Long-acting Beta2-adrenergic Agonist.
a Randomized subjects who had taken at least 1 dose of study drug. Planned treatment used for analysis.
b Estimated using a Cox proportional hazards model for time to first event with baseline hazards stratified by each of the 3 trials.
c Number of subjects with an event that occurred within 6 months after the first use of study drug or 7 days after the last date of study drug, whichever date was later. Subjects may have had one or more events, but only the first event was counted for analysis. A single, blinded, independent, joint adjudication committee determined whether events were asthma related.
Salmeterol Multicenter Asthma Research Trial (SMART)
A 28-week, placebo-controlled, U.S. trial that compared the safety of salmeterol with placebo, each added to usual asthma therapy, showed an increase in asthma-related deaths in subjects receiving salmeterol (13/13,176 in subjects treated with salmeterol versus 3/13,179 in subjects treated with placebo; relative risk: 4.37 [95% CI: 1.25, 15.34]). Use of background ICS was not required in SMART. The increased risk of asthma-related death is considered a class effect of LABA monotherapy.
Not for Acute Use: TRELEGY ELLIPTA should not be used for the relief of acute symptoms of COPD or asthma (i.e., as rescue therapy for the treatment of acute episodes of bronchospasm). Patients should be prescribed a rapid onset, short duration inhaled bronchodilator (e.g., salbutamol) to relieve acute symptoms such as shortness of breath, and advised to have this available for use at all times.
When beginning treatment with TRELEGY ELLIPTA, patients who have been taking a rapid onset, short duration, inhaled bronchodilator on a regular basis should be instructed to discontinue the regular use of these drugs and use them only for symptomatic relief if they develop acute symptoms while taking TRELEGY ELLIPTA.
Deterioration of Disease and Acute Episodes: TRELEGY ELLIPTA should not be initiated in patients with acutely deteriorating COPD or asthma which may be a life-threatening condition. The use of TRELEGY ELLIPTA in this setting has not been studied and is not considered appropriate.
COPD or asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If TRELEGY ELLIPTA no longer controls symptoms of bronchoconstriction, the patient’s inhaled, short-acting bronchodilator becomes less effective or the patient needs more inhalation of a short-acting bronchodilator than usual, these may be markers of deterioration of disease. In this setting, a re-evaluation of the patient and the treatment regimen should be undertaken at once.
Asthma-related adverse events and exacerbations may occur during treatment with TRELEGY ELLIPTA.
Patients should be advised to continue treatment and seek medical advice if symptoms remain uncontrolled or worsen after initiation of therapy with TRELEGY ELLIPTA.
Patients should not stop therapy with TRELEGY ELLIPTA without physician supervision since symptoms may recur after discontinuation.
Excessive use and use with other LABA and LAMA products: TRELEGY ELLIPTA should not be used more often or at higher doses than recommended.
TRELEGY ELLIPTA should not be administered concomitantly with other medicines containing a long-acting beta2-adrenergic agonist (e.g., salmeterol, formoterol fumarate, indacaterol, olodaterol), or a long-acting muscarinic antagonist (e.g., tiotropium, glycopyrronium, aclidinium, umeclidinium) for any reason, as an overdose may result. Clinically significant cardiovascular effects and fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs.
Anticholinergic Effects: Consistent with its antimuscarinic activity, TRELEGY ELLIPTA should be used with caution in patients with narrow-angle glaucoma (see 7 WARNINGS AND PRECAUTIONS, Ophthalmologic) or urinary retention (see 7 WARNINGS AND PRECAUTIONS, Renal) since worsening of these conditions may occur.
Cardiovascular
Cardiovascular effects, such as cardiac arrhythmias, e.g., atrial fibrillation and tachycardia, may be seen after the administration of sympathomimetic agents and muscarinic receptor antagonists, including TRELEGY ELLIPTA. In case such effects occur, treatment may need to be discontinued.
Clinically significant cardiovascular effects and fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs. Cardiovascular effects such as tachycardia, arrhythmia, palpitations, myocardial ischemia, angina pectoris, hypertension or hypotension have been associated with use of beta-adrenergic agonists. In addition, beta-agonists have been reported to produce electrocardiographic changes, such as flattening of the T wave, prolongation of the QTc interval, and ST segment depression. Like all products containing sympathomimetic agents, TRELEGY ELLIPTA should therefore be used with caution in patients with unstable or life-threatening cardiovascular disease, especially coronary insufficiency, cardiac arrhythmias (including tachyarrhythmias), or hypertension.
Electrocardiography: As with other beta2-agonists, caution is recommended if TRELEGY ELLIPTA is administered to patients with a known history of QTc prolongation, risk factors for torsade de pointes (e.g., hypokalemia), or patients who are taking medications known to prolong the QTc interval (see 9.2 Drug Interactions Overview; and 10.2 Pharmacodynamics).
Hemodynamics: Like other beta2-agonists, vilanterol can produce clinically significant cardiovascular effects in some patients as measured by an increase in pulse rate, systolic or diastolic blood pressure, or cardiac arrhythmias such as atrial fibrillation, supraventricular tachycardia and extrasystoles (see 8 ADVERSE REACTIONS and 10 CLINICAL PHARMACOLOGY). If such effects occur, TRELEGY ELLIPTA may need to be discontinued.
Driving and Operating Machinery
There have been no studies investigating the effect of TRELEGY ELLIPTA on the ability to perform tasks that require judgment, motor or cognitive skills. The occurrence of headache or blurred vision may influence the ability to drive or to use machinery.
Ear/Nose/Throat
Localized infections of the mouth and pharynx with Candida albicans, which are associated with the use of inhaled glucocorticosteroids, have occurred in patients treated with TRELEGY ELLIPTA during clinical studies. Patients should therefore be advised to rinse their mouth with water (without swallowing) after inhalation of TRELEGY ELLIPTA to reduce the risk of oropharyngeal candidiasis.
When such an infection develops, it should be treated with appropriate local or systemic (i.e., oral) antifungal therapy while treatment with TRELEGY ELLIPTA continues. However, at times, therapy with TRELEGY ELLIPTA may need to be interrupted for the treatment of severe infections (see 9.4 Drug-Drug Interactions).
Endocrine and Metabolism
Systemic effects of inhaled corticosteroids may occur, particularly at high doses prescribed for prolonged periods. These effects are much less likely to occur with inhaled corticosteroids than with oral corticosteroids. Possible systemic effects include: Cushing’s syndrome, Cushingoid features, hypothalamic-pituitary-adrenal (HPA) axis suppression, growth retardation in children and adolescents (in asthma), a decrease in bone mineral density (BMD), cataracts, glaucoma, and central serous chorioretinopathy.
Hypercorticism and Adrenal Suppression: Inhaled fluticasone furoate is absorbed into the circulation and can be systemically active (see 10.2 Pharmacodynamics). Exceeding the recommended dosage or co-administration with a strong cytochrome P450 3A4 (CYP3A4) inhibitor may result in HPA dysfunction (see 9.4 Drug-Drug Interactions).
It is possible that systemic corticosteroid effects such as hypercorticism and adrenal suppression (including adrenal crisis) may appear in a small number of patients who are sensitive to these effects. In light of the possibility of systemic absorption of inhaled corticosteroids, patients treated with TRELEGY ELLIPTA should be observed carefully for any evidence of systemic corticosteroid effects. Particular care should be taken in observing patients postoperatively or during periods of stress for evidence of inadequate adrenal response. If such effects occur, appropriate therapy should be considered.
Systemic Steroid Replacement by Inhaled Steroid: Particular care is needed for patients who have been transferred from systemically active corticosteroids to inhaled corticosteroids because deaths due to adrenal insufficiency have occurred in patients with asthma during and after transfer from systemic corticosteroids to less systemically available inhaled corticosteroids. After withdrawal from systemic corticosteroids, a number of months are required for recovery of HPA function.
Patients who have been previously maintained on 20 mg or more of prednisone (or its equivalent) may be most susceptible, particularly when their systemic corticosteroids have been almost completely withdrawn. During this period of HPA suppression, patients may exhibit signs and symptoms of adrenal insufficiency when exposed to trauma, surgery, or infection (particularly gastroenteritis) or other conditions associated with severe electrolyte loss. Although TRELEGY ELLIPTA may control COPD or asthma symptoms during these episodes, in recommended doses it supplies less than normal physiological amount of glucocorticoid systemically and does NOT provide the mineralocorticoid activity that is necessary for coping with these emergencies.
During periods of stress, a severe asthma attack, or a severe COPD exacerbation, patients who have been withdrawn from systemic corticosteroids should be instructed to resume oral corticosteroids immediately and to contact their physicians for further instruction. These patients should also be instructed to carry a warning card indicating that they may need supplementary systemic corticosteroids during periods of stress, a severe asthma attack, or severe COPD exacerbation.
Patients requiring oral corticosteroids should be weaned slowly from systemic corticosteroid use after transferring to TRELEGY ELLIPTA. Lung function (mean forced expiratory volume in 1 second [FEV1]), beta-agonist use, and COPD or asthma symptoms should be carefully monitored during withdrawal of oral corticosteroids. In addition, patients should be observed for signs and symptoms of adrenal insufficiency, such as fatigue, lassitude, weakness, nausea and vomiting, and hypotension.
Transfer of patients from systemic corticosteroid therapy to TRELEGY ELLIPTA may unmask allergic conditions previously suppressed by the systemic corticosteroid therapy (e.g., rhinitis, conjunctivitis, eczema, arthritis, eosinophilic conditions).
During withdrawal from oral corticosteroids, some patients may experience symptoms of systemically active corticosteroid withdrawal (e.g., joint and/or muscular pain, lassitude, depression), despite maintenance or even improvement of respiratory function.
Reduction in Bone Mineral Density: Decreases in bone mineral density (BMD) have been observed with long-term administration of products containing inhaled corticosteroids. Patients with major risk factors for decreased bone mineral content, such as prolonged immobilization, family history of osteoporosis, postmenopausal status, tobacco use, advanced age, poor nutrition, or chronic use of drugs that can reduce bone mass (e.g., anticonvulsants, oral corticosteroids) should be monitored and treated with established standards of care. Since patients with COPD often have multiple risk factors for reduced BMD, assessment of BMD is recommended prior to initiating TRELEGY ELLIPTA and periodically thereafter. If significant reductions in BMD are seen and TRELEGY ELLIPTA is still considered medically important for that patient’s COPD therapy, use of medication to treat or prevent osteoporosis should be strongly considered.
Effect on Growth: Inhaled corticosteroids may cause a reduction in growth velocity when administered to children and adolescents (see 10.3 Pharmacokinetics, Special Populations and Conditions).
Hypokalemia and Hyperglycemia: Beta-adrenergic agonist medications may produce significant hypokalemia in some patients, which has the potential to produce adverse cardiovascular effects. The decrease in serum potassium is usually transient, not requiring supplementation. TRELEGY ELLIPTA should be used with caution in patients predisposed to low levels of serum potassium. In patients with severe COPD, hypokalemia may be potentiated by hypoxia and concomitant treatment (see 9 DRUG INTERACTIONS), which may increase the susceptibility to cardiac arrhythmias.
Beta-agonist medications may produce transient hyperglycemia in some patients.
Co-existing Conditions: TRELEGY ELLIPTA, like all medications containing sympathomimetic amines, should be used with caution in patients with convulsive disorders or thyrotoxicosis and in those who are unusually responsive to sympathomimetic amines. Doses of the rapid onset, short-duration, beta2-adrenoceptor agonist salbutamol, when administered intravenously, have been reported to aggravate pre-existing diabetes mellitus and ketoacidosis.
Hematologic
Eosinophilic Conditions: In rare cases, patients on inhaled corticosteroids may present with systemic eosinophilic conditions, with some patients presenting with clinical features of vasculitis consistent with eosinophilic granulomatosis with polyangiitis (EGPA), formerly known as Churg-Strauss syndrome, a condition that is often treated with systemic corticosteroid therapy. These events usually, but not always, have been associated with the reduction and/or withdrawal of oral corticosteroid therapy following the introduction of inhaled corticosteroids. Physicians should be alerted to eosinophilia, vasculitic rash, worsening pulmonary symptoms, cardiac complications, and/or neuropathy presenting in their patients. A causal relationship between inhaled corticosteroids and these underlying conditions has not been established.
Hepatic/Biliary/Pancreatic
Hepatic Impairment: TRELEGY ELLIPTA has not been studied in patients with hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment, Hepatic Insufficiency). Information on the individual components is provided below.
Fluticasone Furoate/Vilanterol
Fluticasone furoate systemic exposure increased by up to 3-fold in subjects with mild, moderate and severe hepatic impairment. Patients should be monitored for corticosteroid-related systemic effects. For patients with moderate to severe hepatic impairment, the 100/62.5/25 mcg dose should be used (see 10.3 Pharmacokinetics, Special Populations and Conditions, Hepatic Insufficiency). Hepatic impairment had no effect on vilanterol systemic exposure.
Umeclidinium
Subjects with moderate hepatic impairment (Child-Pugh score of 7-9) showed no relevant increase in systemic exposure to umeclidinium (Cmax and AUC), and no relevant difference in protein binding between subjects with moderate hepatic impairment and healthy volunteers. Umeclidinium has not been evaluated in subjects with severe hepatic impairment.
Hypersensitivity Reactions
Hypersensitivity reactions such as anaphylaxis, angioedema, rash, and urticaria may occur after administration of TRELEGY ELLIPTA. If signs suggesting allergic reactions (in particular, difficulties in breathing or swallowing, swelling of tongue, lips and face, urticaria, skin rash) occur, discontinue TRELEGY ELLIPTA. The patient should NOT be re-challenged with TRELEGY ELLIPTA if this is identified as the cause of the hypersensitivity reaction (see 2 CONTRAINDICATIONS).
There have been reports of anaphylactic reactions in patients with severe milk protein allergy after inhalation of other powder medications containing lactose; therefore, patients with severe milk protein allergy should not use TRELEGY ELLIPTA (see 2 CONTRAINDICATIONS).
Immune
Patients who are using drugs that suppress the immune system are more susceptible to infections than healthy individuals. Chickenpox and measles, for example, can have a more serious or even fatal course in susceptible patients using corticosteroids. In such patients who have not had these diseases or been properly immunized, particular care should be taken to avoid exposure. If a patient is exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) may be indicated. If a patient is exposed to measles, prophylaxis with pooled intramuscular immunoglobulin (IG) may be indicated. If chickenpox develops, treatment with antiviral agents may be considered.
It is important that even mild chest infections be treated immediately since COPD patients may be more susceptible to damaging lung infections than healthy individuals. Patients should be instructed to contact their physician as soon as possible if they suspect an infection.
Physicians should recommend that patients receive an annual influenza vaccination.
As with all medications containing a corticosteroid, TRELEGY ELLIPTA should be administered with caution, and only if necessary, in patients with active or quiescent tuberculosis infections of the respiratory tract; chronic or untreated infections such as systemic fungal, bacterial, viral, or parasitic; or ocular herpes simplex.
Monitoring and Laboratory Tests
Potentially serious hypokalemia has been observed with other beta-agonist therapies, which may increase susceptibility to cardiac arrhythmias. It is therefore recommended that serum potassium levels be monitored in patients predisposed to low levels of serum potassium.
Due to the hyperglycemic effect observed with other beta-agonists, additional blood glucose monitoring is recommended in diabetic patients.
For patients at risk, monitoring of bone and ocular effects (cataract, glaucoma, and central serous chorioretinopathy) should also be considered in patients receiving maintenance therapy with TRELEGY ELLIPTA.
Patients with hepatic impairment should be monitored for corticosteroid effects due to potentially increased systemic exposure of fluticasone furoate.
Ophthalmologic
Glaucoma and increased intraocular pressure have been reported in patients following the long-term administration of inhaled corticosteroids or with use of inhaled anticholinergics. Cataracts have also been reported in patients following the long-term administration of inhaled corticosteroids.
Long-term administration of inhaled corticosteroids may result in central serous chorioretinopathy (CSCR).
TRELEGY ELLIPTA, like other antimuscarinic-containing products, should be used with caution in patients with narrow-angle glaucoma. Prescribers and patients should also be alert for signs and symptoms of acute narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a healthcare professional immediately if any of these signs or symptoms develops.
Close monitoring is warranted in patients with a change in vision or with a history of increased intraocular pressure, narrow- or open-angle glaucoma, cataracts, and/or CSCR.
Renal
TRELEGY ELLIPTA, like other antimuscarinic-containing products, should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of urinary retention (e.g., difficulty passing urine, painful urination), especially in patients with prostatic hyperplasia or bladder-neck obstruction. Instruct patients to consult a healthcare professional immediately if any of these signs or symptoms develops.
Respiratory
Paradoxical Bronchospasm: As with other inhalation therapies, paradoxical bronchospasm may occur with an immediate increase in wheezing after dosing, and may be life-threatening. This should be treated immediately with a rapid onset, short duration inhaled bronchodilator such as salbutamol. Treatment with TRELEGY ELLIPTA should be discontinued immediately, the patient assessed and alternative therapy instituted if necessary.
Pneumonia:
COPD: In line with the known class effect of inhaled corticosteroids, pneumonia events (including pneumonias resulting in hospitalization) were observed in patients with COPD receiving TRELEGY ELLIPTA. In some instances, fatal events of pneumonia have been reported with use of inhaled corticosteroid fluticasone furoate-containing drugs, including TRELEGY ELLIPTA (see 8 ADVERSE REACTIONS). Physicians should remain vigilant for the possible development of pneumonia in patients with COPD, as the clinical features of such infections overlap with the symptoms of COPD exacerbations. Risk factors for pneumonia in patients with COPD receiving inhaled corticosteroid-containing drugs include current smokers, patients with a history of prior pneumonia, patients with low body mass index and patients with severe COPD. These factors should be considered when TRELEGY ELLIPTA is prescribed, and treatment should be re-evaluated if pneumonia occurs.
There is no conclusive clinical evidence for intra-class differences in the magnitude of the pneumonia risk among inhaled corticosteroid products.
Asthma: An increased incidence of pneumonia in patients with asthma receiving higher doses of TRELEGY ELLIPTA cannot be excluded. This is based on clinical experience with fluticasone furoate/vilanterol, where there was a trend toward an increased risk of pneumonia for fluticasone furoate/vilanterol 200/25 mcg compared with fluticasone furoate/vilanterol 100/25 mcg and placebo.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies with TRELEGY ELLIPTA or the individual components, fluticasone furoate, umeclidinium and vilanterol, in pregnant women. Corticosteroids and beta2-agonists have been shown to be teratogenic in laboratory animals when administered systemically at relatively low dosage levels. Because animal studies are not always predictive of human response, TRELEGY ELLIPTA should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus. Women should be advised to contact their physician if they become pregnant while taking TRELEGY ELLIPTA.
Use in Labour and Delivery: There are no adequate and well-controlled human studies that have investigated the effects of TRELEGY ELLIPTA or the individual components, fluticasone furoate, umeclidinium and vilanterol, during labour and delivery. Because beta-agonists may potentially interfere with uterine contractility, TRELEGY ELLIPTA should be used during labour only if the potential benefit justifies the potential risk.
7.1.2 Breast-feeding
It is not known whether fluticasone furoate, umeclidinium or vilanterol are excreted in human breast milk. However, other corticosteroids and beta2-agonists have been detected in human milk. Furthermore, other muscarinic antagonists (including metabolites) are excreted into the milk of lactating rats. A risk to breastfed newborns/infants cannot be excluded. Therefore, the use of TRELEGY ELLIPTA by breast-feeding women should only be considered if the expected benefit to the woman is greater than any possible risk to the infant.
7.1.3 Pediatrics
Pediatrics (<18 years of age): TRELEGY ELLIPTA is not indicated for use in children and therefore should not be used in patients under 18 years of age (see 4.2 Recommended Dose and Dosage Adjustment, Pediatrics).
7.1.4 Geriatrics
Geriatrics (≥65 years of age): Based on the available data, there is no need to adjust the dose in elderly patients, but greater sensitivity of some older individuals cannot be ruled out (see 4.2 Recommended Dose and Dosage Adjustment, Geriatrics).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The overall safety profile of TRELEGY ELLIPTA was generally consistent with the known pharmacologic class effects of ICSs, LAMAs and/or LABAs. In trials in adult subjects with COPD or asthma, the most common adverse reaction was nasopharyngitis (see 8.2 Clinical Trial Adverse Reactions).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Clinical Trial Adverse Reactions in Subjects with COPD
The safety profile of TRELEGY ELLIPTA (ICS/LAMA/LABA) in subjects with COPD is based on data from two phase III clinical studies (CTT116853 and CTT116855).
Study CTT116853 included 911 patients with COPD who received TRELEGY ELLIPTA 100/62.5/25 mcg once daily for up to 24 weeks, of whom 210 patients received TRELEGY ELLIPTA 100/62.5/25 mcg once daily for up to 52 weeks, during a phase III clinical study versus an active comparator (ICS/LABA) administered twice daily (see Table 3).
Study CTT116855 included 4,151 patients with COPD who received TRELEGY ELLIPTA 100/62.5/25 mcg once daily for up to 52 weeks during a phase III clinical study versus one of two active comparators (ICS/LABA or LAMA/LABA) (see Table 4).
Adverse reactions detected during these clinical trials are listed by MedDRA system organ class.
| Table 3 Adverse Reactions with ≥1% Incidence with TRELEGY ELLIPTA following 24 Weeks and 52 Weeks of Treatment in Study CTT116853 | ||||||||||||
System Organ Class Preferred term | TRELEGY ELLIPTA 100/62.5/25 mcg N = 911 n (%) 24 weeks | ICS/LABA N = 899 n (%) 24 weeks | TRELEGY ELLIPTA 100/62.5/25 mcg N = 210 n (%) 52 weeks | ICS/LABA N = 220 n (%) 52 weeks | ||||||||
| Infections and Infestations | ||||||||||||
| Nasopharyngitis | 64 (7) | 43 (5) | 23 (11) | 22 (10) | ||||||||
| Upper respiratory tract infection | 20 (2) | 19 (2) | 6 (3) | 10 (5) | ||||||||
| Pneumonia | 19 (2) | 7 (<1) | 4 (2) | 4 (2) | ||||||||
| Pharyngitis | 15 (2) | 9 (1) | 5 (2) | 1 (<1) | ||||||||
| Rhinitis | 10 (1) | 11 (1) | 3 (1) | 5 (2) | ||||||||
| Influenza | 10 (1) | 8 (<1) | 2 (<1) | 0 | ||||||||
| Viral respiratory tract infection | 2 (<1) | 4 (<1) | 3 (1) | 3 (1) | ||||||||
| Nervous system disorders | ||||||||||||
| Headache | 44 (5) | 53 (6) | 17 (8) | 22 (10) | ||||||||
| Musculoskeletal and connective tissue disorders | ||||||||||||
| Back pain | 19 (2) | 18 (2) | 4 (2) | 5 (2) | ||||||||
| Arthralgia | 17 (2) | 13 (1) | 5 (2) | 6 (3) | ||||||||
| Respiratory, thoracic, and mediastinal disorders | ||||||||||||
| Cough | 10 (1) | 10 (1) | 3 (1) | 3 (1) | ||||||||
| Oropharyngeal pain | 9 (<1) | 10 (1) | 6 (3) | 1 (<1) | ||||||||
Table 4 Adverse Reactions with ≥1% Incidence with TRELEGY ELLIPTA following up to 52 Weeks of Treatment in Study CTT116855
System Organ Class Preferred term | TRELEGY ELLIPTA 100/62.5/25 mcg N = 4,151 n (%) | ICS/LABA N = 4,134 n (%) | LAMA/LABA N = 2,070 n (%) |
Gastrointestinal Disorders Constipation Infections and Infestations Upper respiratory tract infection Pneumonia Oral candidiasis Bronchitis Influenza Sinusitis Urinary Tract Infection Pharyngitis Rhinitis Musculoskeletal and connective tissue disorders Back pain Arthralgia Nervous system disorders Headache Respiratory, thoracic, and mediastinal disorders Cough Oropharyngeal pain | 65 (2) 299 (7) 298 (7) 161 (4) 152 (4) 117 (3) 104 (3) 92 (2) 82 (2) 89 (2) 148 (4) 122 (3) 233 (6) 145 (3) 99 (2) | 63 (2) 283 (7) 264 (6) 146 (4) 130 (3) 102 (2) 98 (2) 86 (2) 81 (2) 69 (2) 140 (3) 86 (2) 198 (5) 117 (3) 71 (2) | 16 (<1) 117 (6) 93 (4) 41 (2) 73 (4) 50 (2) 45 (2) 35 (2) 48 (2) 33 (2) 83 (4) 46 (2) 103 (5) 58 (3) 39 (2) |
Pneumonia
In study CTT116853, 1,810 patients with COPD with mean post-bronchodilator screening FEV1 45% of predicted, standard deviation [SD] 13%, and a history of exacerbations were treated with TRELEGY ELLIPTA 100/62.5/25 mcg or an active comparator (ICS/LABA). There was a higher incidence of pneumonia events reported up to 24 weeks in patients receiving TRELEGY ELLIPTA 100/62.5/25 mcg (2%) than in patients receiving ICS/LABA (<1%). Pneumonia which required hospitalization occurred in 1% of patients receiving TRELEGY ELLIPTA 100/62.5/25 mcg and <1% of patients receiving ICS/LABA up to 24 weeks. One fatal case of pneumonia was reported in a patient who received TRELEGY ELLIPTA 100/62.5/25 mcg. In the subset of 430 patients treated for up to 52 weeks, the incidence of pneumonia events reported in both TRELEGY ELLIPTA 100/62.5/25 mcg and the ICS/LABA arms was equal at 2%.
In study CTT116855, 10,355 patients with COPD with mean post-bronchodilator screening FEV1 46% of predicted, SD 15%, and a history of 1 or more moderate or severe exacerbations within the prior 12 months were treated with TRELEGY ELLIPTA 100/62.5/25 mcg or one of two active comparators (ICS/LABA or LAMA/LABA) up to 52 weeks. The incidence of pneumonia (adverse events of special interest) was 8% for TRELEGY ELLIPTA 100/62.5/25 mcg, 7% for ICS/LABA, and 5% for LAMA/LABA. Fatal pneumonia occurred in 12 of 4,151 patients (3.5 per 1,000 patient-years) receiving TRELEGY ELLIPTA
100/62.5/25 mcg, 5 of 4,134 patients (1.7 per 1,000 patient-years) receiving ICS/LABA, and 5 of 2,070 patients (2.9 per 1,000 patient-years) receiving LAMA/LABA.
Clinical Trial Adverse Reactions in Subjects with Asthma
The safety profile of TRELEGY ELLIPTA (ICS/LAMA/LABA) in adult subjects with asthma is based on one Phase III clinical study (205715) with a variable treatment duration of 24 to 52 weeks.
Study 205715 included 814 adult subjects with asthma who received TRELEGY ELLIPTA 100/62.5/25 mcg or 200/62.5/25 mcg once daily for up to 52 weeks versus an active comparator (fluticasone furoate/vilanterol) administered once daily (see Table 5). Adverse reactions observed for the groups treated with TRELEGY ELLIPTA were similar to those observed for the fluticasone furoate/vilanterol arms.
Adverse reactions detected during study 205715 are listed by MedDRA system organ class.
| Table 5 Adverse Reactions with ≥1% Incidence with TRELEGY ELLIPTA following up to 52 Weeks of Treatment in Study 205715 | |||||||||||||
System Organ Class Preferred term | TRELEGY ELLIPTA 200/62.5/25 mcg N = 408 n (%) | TRELEGY ELLIPTA 100/62.5/25 mcg N = 406 n (%) | FF/VI 200/25 mcg N = 406 n (%) | FF/VI 100/25 mcg N = 407 n (%) | |||||||||
| Infections and Infestations | |||||||||||||
| Nasopharyngitis | 51 (13) | 60 (15) | 53 (13) | 63 (15) | |||||||||
Upper respiratory tract infection Bronchitis Viral respiratory tract infection Sinusitis Viral upper respiratory tract infection | 19 (5) 22 (5) 9 (2) 12 (3) 9 (2) | 15 (4) 15 (4) 10 (2) 6 (1) 6 (1) | 13 (3) 19 (5) 7 (2) 9 (2) 11 (3) | 21 (5) 14 (3) 11 (3) 9 (2) 6 (1) | |||||||||
| Pharyngitis | 9 (2) | 9 (2) | 14 (3) | 8 (2) | |||||||||
| Urinary tract infection | 7 (2) | 3 (<1) | 1 (<1) | 5 (1) | |||||||||
| Rhinitis | 6 (1) | 10 (2) | 8 (2) | 11 (3) | |||||||||
| Influenza | 6 (1) | 15 (4) | 9 (2) | 13 (3) | |||||||||
| Pneumonia | 4 (<1) | 5 (1) | 7 (2) | 7 (2) | |||||||||
| Respiratory tract infection | 4 (<1) | 6 (1) | 3 (<1) | 6 (1) | |||||||||
| Nervous system disorders | |||||||||||||
| Headache | 19 (5) | 36 (9) | 23 (6) | 30 (7) | |||||||||
| Musculoskeletal and connective tissue disorders | |||||||||||||
| Back pain | 9 (2) | 13 (3) | 6 (1) | 16 (4) | |||||||||
| Respiratory, thoracic, and mediastinal disorders | |||||||||||||
| Oropharyngeal pain | 6 (1) | 6 (1) | 4 (<1) | 4 (<1) | |||||||||
| Cough | 6 (1) | 3 (<1) | 6 (1) | 5 (1) | |||||||||
| Dysphonia | 6 (1) | 6 (1) | 8 (2) | 5 (1) | |||||||||
FF/VI = Fluticasone Furoate/Vilanterol
Pneumonia
The incidence of pneumonia events requiring hospitalisation was similar in the TRELEGY ELLIPTA and fluticasone furoate/vilanterol groups (<1% for all groups). There were no fatal pneumonia events.
8.3 Less Common Clinical Trial Adverse Reactions
COPD
In addition to adverse reactions reported in Table 3 and Table 4, adverse reactions occurring at a rate of less than 1% in subjects with COPD receiving TRELEGY ELLIPTA included:
Cardiac disorders: supraventricular tachyarrhythmias, tachycardia, atrial fibrillation
Gastrointestinal Disorders: dry mouth
Infections and infestations: oropharyngeal candidiasis
Musculoskeletal and connective tissue disorders: fractures
Respiratory, thoracic, and mediastinal disorders: dysphonia
Asthma
In addition to adverse reactions reported in Table 5, adverse reactions occurring at a rate of less than 1% in subjects with asthma receiving TRELEGY ELLIPTA included:
Cardiac disorders: supraventricular tachyarrhythmias, tachycardia, atrial fibrillation
Gastrointestinal disorders: constipation, dry mouth
Infections and infestations: candidiasis of mouth and throat
Musculoskeletal and connective: arthralgia, fractures
Nervous system disorders: dysgeusia
8.5 Post-Market Adverse Reactions
The following relevant adverse reactions have been identified from post-approval use of TRELEGY ELLIPTA. Because these reactions are reported voluntarily from a population of uncertain size, it is not possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Cardiac disorders: Palpitations
Eye Disorders: vision blurred, glaucoma, eye pain, intraocular pressure increased
Immune System Disorders: hypersensitivity reactions including anaphylaxis, angioedema, urticaria and rash
Metabolism and nutrition disorders: Hyperglycaemia
Musculoskeletal and connective tissue disorders: Muscle spasms
Nervous system disorders: Tremor
Psychiatric disorders: Anxiety
Renal and Urinary Disorders: urinary retention, dysuria
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Drugs Known to Prolong the QTc Interval
As with other beta2-adrenergic agonists, TRELEGY ELLIPTA should be administered with caution to patients treated with monoamine oxidase inhibitors, tricyclic antidepressants, or drugs known to prolong the QT interval, as any effect of these on the QT interval may be potentiated. Drugs known to prolong the QT-interval may increase the risk of ventricular arrhythmia (see 7 WARNINGS AND PRECAUTIONS and 10 CLINICAL PHARMACOLOGY).
Sympathomimetic Agents
Concomitant administration of other sympathomimetic agents (alone or as part of combination therapy) may potentiate the undesirable effects of TRELEGY ELLIPTA (see 7 WARNINGS AND PRECAUTIONS).
Treatments Leading to Hypokalaemia
Beta-agonists have been associated with reductions in serum potassium levels. Concomitant treatment with xanthine derivatives, oral corticosteroids (e.g., prednisone), or non-potassium sparing diuretics may potentiate any hypokalemic effect of adrenergic agonists (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism, Hypokalemia and Hyperglycemia).
Beta-Adrenergic Blockers
Beta-adrenergic blockers may weaken or antagonize the effect of beta2-adrenergic agonists, such as vilanterol. Therefore, TRELEGY ELLIPTA should not be given together with beta-adrenergic blockers (including eye-drops) unless there are compelling reasons for their use. In this setting, cardioselective beta-blockers could be considered, although they should be administered with caution.
Metabolic and transporter based drug interactions
Fluticasone furoate and vilanterol are both substrates of CYP3A4.
Co-treatment of fluticasone furoate with CYP3A4 inhibitors is expected to increase the risk of systemic side effects (see Table 6). Co-administration should be avoided unless the benefit outweighs the increased risk of systemic corticosteroid side effects, in which case patients should be monitored for systemic corticosteroid side effects.
Co-administration of repeat dose ketoconazole (a strong CYP3A4 inhibitor and P-gp inhibitor) with fluticasone furoate/vilanterol 200/25 mcg resulted in increased mean fluticasone furoate AUC(0-24) and Cmax by 36% and 33%, respectively, and increased mean vilanterol AUC(0-t’) and Cmax by 65% and 22%, respectively. The increase in fluticasone furoate exposure was associated with a 27% reduction in weighted mean serum cortisol (0 to 24 hours). The increase in vilanterol exposure was not associated with an increase in beta-agonist-related systemic effects on heart rate or blood potassium but was associated with a slight increase in QTcF interval. Administration of inhaled vilanterol 25 mcg alone with ketoconazole 400 mg resulted in a 1.9-fold increase in vilanterol systemic exposure as measured by AUC(0-t), but there was no change in Cmax. The increase in AUC was not associated with effects on heart rate, blood potassium, and QTcF. Therefore, caution is required with the co-administration of TRELEGY ELLIPTA and ketoconazole or other potent CYP3A4 inhibitors.
Umeclidinium is a substrate of CYP2D6; however, umeclidinium pharmacokinetics were not significantly affected in a population of CYP2D6 poor metabolizers (10.3 Pharmacokinetics).
Fluticasone furoate, umeclidinium and vilanterol are substrates of P-glycoprotein (P-gp). The effect of the moderate P-gp transporter inhibitor verapamil (240 mg once daily) on the steady-state pharmacokinetics of umeclidinium and vilanterol administered together and umeclidinium administered alone was assessed in healthy volunteers. An approximately 1.4-fold increase in umeclidinium AUC was observed with no effect on vilanterol AUC. No effect of verapamil was observed on umeclidinium or vilanterol Cmax. A decrease in blood potassium, an increase in QTc interval and an increased number of supraventricular tachycardia events occurred with co-administration with verapamil. No P-gp inhibitor drug interaction studies have been conducted with fluticasone furoate alone or in combination with vilanterol.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 6 Established or Potential Drug-Drug Interactions
| Drug Type | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| CYP3A4 inhibitors | CT | May inhibit the metabolism of, and increase the systemic exposure to, fluticasone furoate and vilanterol. | Caution should be exercised when considering co-administration with ketoconazole and other known strong CYP3A4 inhibitors (e.g., itraconazole, voriconazole, ritonavir, indinavir, lopinavir, nelfinavir, saquinavir, clarithromycin, atazanavir, cobicistat-containing products). |
| Inhibitors of P-gp | CT | May alter the systemic exposure to umeclidinium and vilanterol resulting in pharmacodynamics effects. | An approximately 1.4-fold increase in umeclidinium AUC was observed with no effect on vilanterol AUC. No effect of verapamil was observed on umeclidinium or vilanterol Cmax. No dose adjustment is warranted. Drug interaction studies with a specific P-gp inhibitor and fluticasone furoate (alone or in combination with vilanterol) have not been conducted. |
| Sympathomimetic agents | T | Potential pharmacodynamics interaction (additive pharmacologic and adverse effects) | Caution is recommended for concomitant use with sympathomimetic agents administered by any route. |
Drugs that prolong the QTc interval Monoamine Oxidase Inhibitors and Tricyclic Antidepressants | T | May result in potentiation of cardiovascular effects of adrenergic agonists with drugs that are known to prolong the QTc interval (increased risk of ventricular arrhythmias). | Caution is recommended for concomitant therapy. |
| Beta-Adrenergic Receptor Blocking Agents (including ophthalmic agents) | T | Beta-blockers not only block the pulmonary effect of beta-agonists, such as vilanterol, but may also produce severe bronchospasm in | If concomitant therapy is required cardioselective beta-blockers could be considered, although they should be administered with caution. |
| Drug Type | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| patients with COPD or asthma. | |||
| Non-Potassium-Sparing Diuretics (i.e., loop or thiazide diuretics) | T | ECG changes and/or hypokalemia can be acutely worsened by beta-agonists, especially when the recommended dose of beta-agonist is exceeded. | Although the clinical significance of these effects is not known, caution is advised in the co-administration of beta-agonists with non-potassium-sparing diuretics. |
| Anticholinergics | T | There is potential for an additive interaction with concomitantly used anticholinergic medications. | Avoid co-administration with other anticholinergic-containing drugs. |
| CYP2D6 inhibitors | T | May alter systemic exposure to umeclidinium resulting in pharmacodynamics effects. | Umeclidinium pharmacokinetics were not significantly affected in a population of CYP2D6 poor metabolizers. No dose adjustment is warranted. |
| Xanthine derivatives | T | Potential pharmacodynamic interaction (increased risk of hypokalemia) | Use with caution in conjunction with beta-agonists. |
| Acetylsalicylic acid | T | Use with caution in conjunction with corticosteroids in hypoprothrombinemia. | |
Legend: CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions with food have not been evaluated. No clinically relevant effect of food would be expected and therefore a food interaction study was not performed.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been evaluated.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been evaluated.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
TRELEGY ELLIPTA contains fluticasone furoate, umeclidinium, and vilanterol. The mechanisms of action described below for the individual components apply to TRELEGY ELLIPTA. These drugs represent three different classes of medications, each having different effects on clinical and physiological indices.
Fluticasone Furoate: Fluticasone furoate is a synthetic trifluorinated corticosteroid with potent, local, anti-inflammatory activity. The precise mechanism through which fluticasone furoate affects COPD and asthma symptoms is not known. Inflammation is an important component in the pathogenesis of COPD and asthma. Corticosteroids have been shown to have a wide range of actions on multiple cell types (e.g., mast cells, eosinophils, neutrophils, basophils, macrophages, lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) involved in inflammation. Specific effects of fluticasone furoate demonstrated in in vitro and in vivo models included activation of the glucocorticoid response element, inhibition of pro-inflammatory transcription factors such as NFkB resulting in inhibition of pro-inflammatory cytokines, and inhibition of antigen-induced lung eosinophilia in sensitized rats. These anti-inflammatory actions of corticosteroids may contribute to their efficacy.
Fluticasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor that is approximately 29.9 times that of dexamethasone and 1.7 times that of fluticasone propionate. Although fluticasone furoate is structurally related to fluticasone propionate, they are distinct chemical entities and do not share common metabolites. In vitro studies have shown that translocation of the glucocorticoid receptor into the cell nucleus (essential for anti-inflammatory activity) is both more rapid and more prolonged with fluticasone furoate compared with fluticasone propionate. Nuclear localization of the glucocorticoid receptor was observed at 30 hours post-exposure with fluticasone furoate but not with fluticasone propionate. The clinical relevance of these findings is unknown.
Umeclidinium: Umeclidinium is a long-acting muscarinic antagonist (LAMA) [also referred to as a long-acting anticholinergic (LAAC)]. It is a quinuclidine derivative that is a muscarinic receptor antagonist with activity across multiple muscarinic cholinergic receptor subtypes. Umeclidinium exerts its 24-hour bronchodilatory activity by competitively inhibiting the binding of acetylcholine with muscarinic acetylcholine receptors on airway smooth muscle. It demonstrates slow reversibility at the human M3 muscarinic receptor subtype in vitro and a long duration of action in vivo when administered directly to the lungs in pre-clinical models.
Vilanterol: Vilanterol is a selective high-affinity long acting beta2-agonist (LABA), with bronchodilatory effects maintained for 24-hours. The pharmacologic effects of beta2-agonists, including vilanterol, are at least in part attributable to stimulation of intracellular adenylate cyclase, the enzyme that catalyzes the conversion of adenosine triphosphate (ATP) to cyclic-3’,5’-adenosine monophosphate (cyclic AMP). Increased cyclic AMP levels cause relaxation of bronchial smooth muscle and inhibition of release of mediators of immediate hypersensitivity from cells, especially from mast cells. Although beta2-receptors are the predominant adrenergic receptors in bronchial smooth muscle and beta1-receptors are the predominant receptors in the heart, there are also beta2-receptors in the human heart comprising 10% to 50% of the total beta-adrenergic receptors. The precise function of these receptors has not been established, but they raise the possibility that even highly selective beta2-agonists may have cardiac effects.
10.2 Pharmacodynamics
Time to Onset of Action
In a study of TRELEGY ELLIPTA (fluticasone furoate/umeclidinium/vilanterol) 100/62.5/25 mcg once daily, serial spirometry measures were obtained from a subgroup of 203 subjects with COPD. On Day 1, 49% of subjects achieved an increase of ≥100 mL over baseline FEV1 at 15 minutes (time of first serial spirometry sample). Median time to onset of action was 26 minutes.
HPA Axis Effects
Effects on HPA-axis function are known to occur with systemic administration of corticosteroids and this systemic side effect has also been reported with inhaled and intranasal corticosteroid use.
Based on both clinical pharmacology and clinical data, inhaled fluticasone furoate at repeat doses up to 400 mcg was not consistently associated with statistically significant decreases in serum or urinary cortisol in healthy subjects. At higher doses, above the therapeutic range, corticosteroid class-related decreases in serum and urine cortisol levels were observed. In line with the increased fluticasone furoate systemic exposure, serum cortisol was reduced by approximately a third in subjects with moderate hepatic impairment after fluticasone furoate/vilanterol 200/25 mcg administration and a similar effect would be anticipated in subjects with severe hepatic impairment at this dose.
Class-Related Beta2-Adrenoceptor Systemic Effects
Class-related systemic effects that are known to occur with systemic administration of beta-agonists include hypokalaemia, hyperglycaemia, and increases in blood pressure, heart rate and the QTc interval. Following inhaled administration these effects are limited by local topical administration in the lung, low clinical doses and first pass metabolism of the swallowed portion of the dose and also tended to diminish on repeat dosing.
The clinical pharmacology data indicate that vilanterol 25 mcg is not associated with clinically significant class-related beta2-adrenoceptor systemic effects. Vilanterol, administered either alone or in combination with fluticasone furoate at doses up to 50 mcg was not associated with clinically relevant or statistically significant effects on blood potassium or blood glucose. Vilanterol 100 mcg was associated with a small decrease in blood potassium (approximately ≤0.1 mmol/L) and a small increase in blood glucose (approximately <1 mmol/L). Vilanterol at doses up to 100 mcg was not consistently associated with clinically relevant or statistically significant effects on blood pressure. Where PD effects were seen, there was no evidence of an increased effect with repeat dosing while some effects showed signs of diminishing.
Cardiovascular Effects
Fluticasone Furoate/Umeclidinium/Vilanterol: The effect of fluticasone furoate/umeclidinium/vilanterol on the QT interval has not been evaluated in a thorough QT (TQT) study.
No clinically relevant effects on the QTc interval were observed on review of centrally read ECGs from 766 subjects with asthma exposed to TRELEGY ELLIPTA for up to 24 weeks, or in a subset of 178 subjects exposed for up to 52 weeks.
No clinically relevant effects on the QTc interval were observed on review of centrally read ECGs from 911 subjects with COPD exposed to fluticasone furoate/umeclidinium/vilanterol for up to 24 weeks, or in a subset of 210 subjects exposed for up to 52 weeks.
The effect of TRELEGY ELLIPTA on cardiac rhythm in subjects diagnosed with COPD was assessed using 24-hour Holter monitoring in a subset of subjects in a 24-week active comparator study: 212 subjects receiving TRELEGY ELLIPTA for 24 weeks were assessed. No clinically meaningful effects on cardiac rhythm were observed following 24 weeks of treatment.
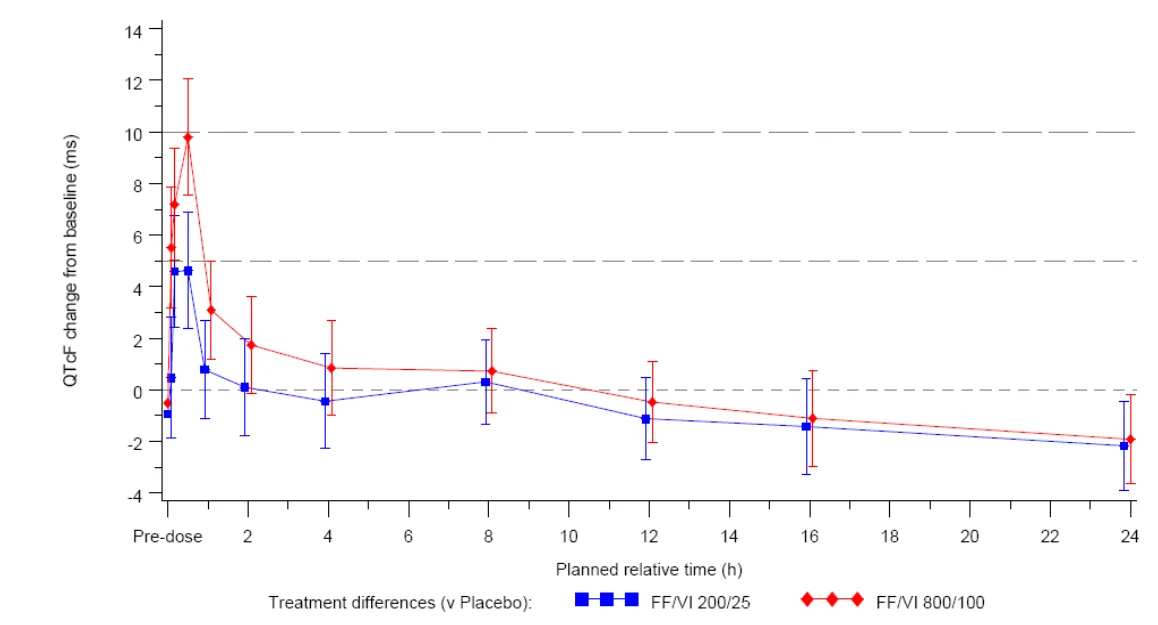
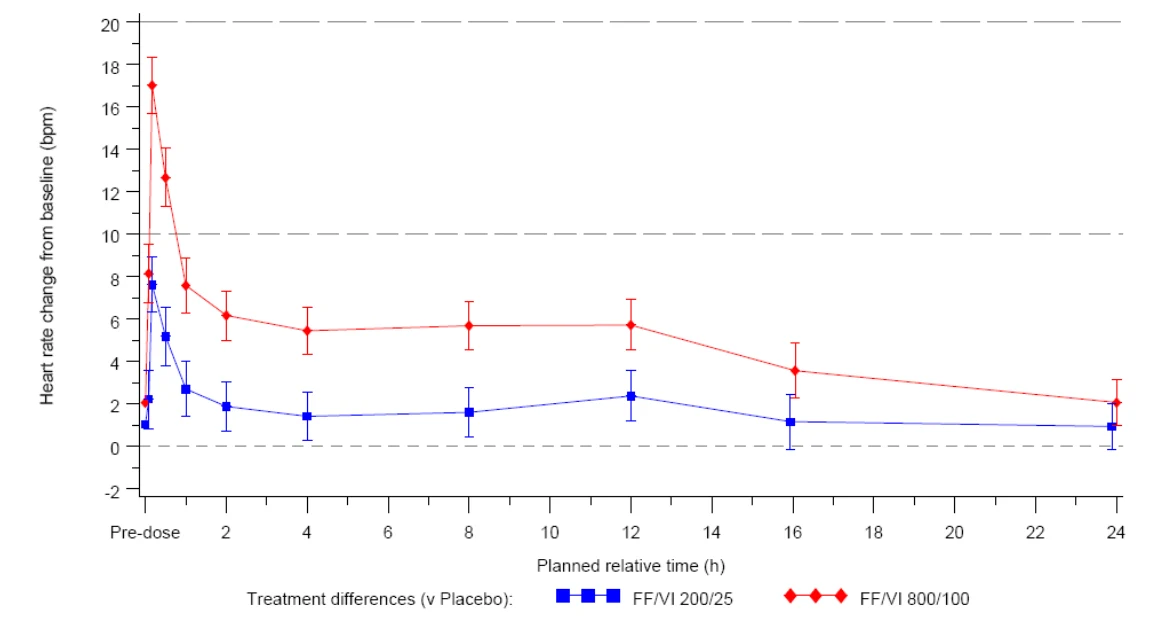
Fluticasone Furoate/Vilanterol: The effect of fluticasone furoate/vilanterol on ECG parameters was investigated in 85 healthy subjects in a double-blind, randomised, placebo- and active- controlled, 4-way crossover study. Fluticasone furoate/vilanterol 200/25 mcg and fluticasone furoate/vilanterol 800/100 mcg were administered once daily for 7 days. The fluticasone furoate/vilanterol dose represented up to 4 times the recommended dose of vilanterol in fluticasone furoate/vilanterol, and a 10 or 12-fold higher vilanterol systemic exposure than seen in patients with asthma and COPD, respectively.
Increases in the QTcF interval were observed that were maximal at 30 min post-dosing. At the 30 min time point, the placebo-adjusted mean changes from baseline in the QTcF interval (ms) were 4.5 (90% CI: 2.1, 6.9) in the fluticasone furoate/vilanterol 200/25 mcg treatment arm and 9.6 (90% CI: 7.2, 12.0) in the fluticasone furoate/vilanterol 800/100 mcg treatment arm.
Figure 1 QTcF Treatment Differences From Placebo: Adjusted Mean Change (and 90% CI) from Baseline by Time (0-24H) on Day 7 – All Subjects Population (FF/VI data only; manually read ECGs)
*QTcF=QT/RR0.33
Increases in heart rate were observed that were maximal at 10 min. At the 10 min time point, the placebo-adjusted mean change from baseline in heart rate (bpm) was 7.6 (90% CI: 6.3, 8.9) in the fluticasone furoate/vilanterol 200/25 mcg treatment arm and 17.0 (90% CI: 15.7, 18.3) in the fluticasone furoate/vilanterol 800/100 mcg treatment arm.
Figure 2 Heart Rate Differences From Placebo: Adjusted Mean Change (and 90% CI) from Baseline by Time (0-24H) on Day 7 – All Subjects Population (FF/VI data only; manually read ECGs)
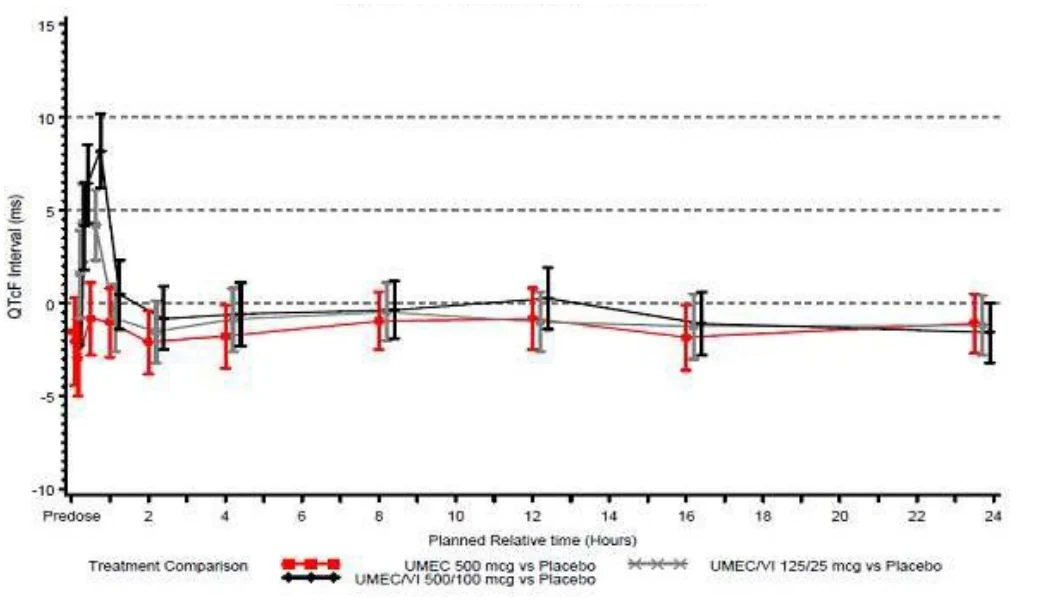
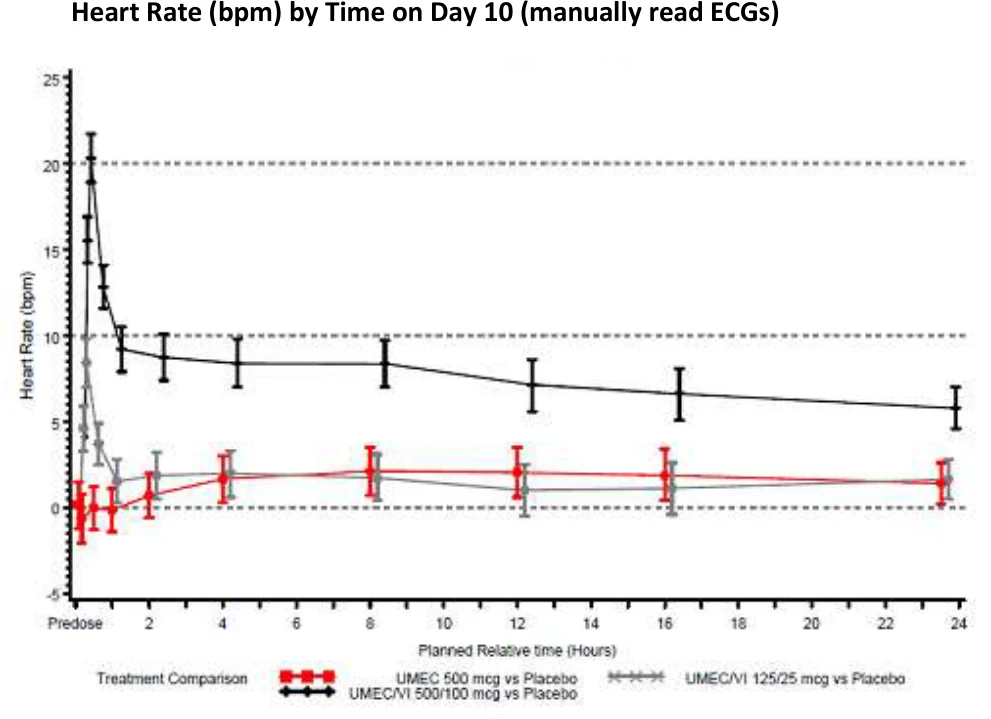
Umeclidinium/Vilanterol: The effect of umeclidinium/vilanterol on ECG parameters was investigated in 103 healthy subjects in a double-blind, randomized, placebo- and active- controlled, incomplete block, crossover study. Umeclidinium alone at a dose of 500 mcg and umeclidinium/vilanterol at supratherapeutic doses of 125/25 mcg (2X/1X therapeutic dose) and 500/100 mcg (8X/4X therapeutic dose) were studied once daily for 10 days.
Increases in the QTcF interval were observed that were maximal at 10 min (umeclidinium/vilanterol 125/25 mcg) and 30 min (umeclidinium/vilanterol 500/100 mcg) post-dosing. The maximal placebo-adjusted mean change in the QTcF interval was 4.3 ms (90% CI: 2.2, 6.4) at 10 min for the 125/25 mcg dose and 8.2 ms (90% CI: 6.2, 10.2) at 30 min for the 500/100 mcg dose.
Umeclidinium 500 mcg alone was not associated with QTc prolongation.
Figure 3 Differences from Placebo (and 90% CIs) in Adjusted Mean Change from Baseline in QTcF (ms) by Time on Day 10 (manually read ECGs)
*QTcF=QT/RR0.33
A dose-dependent increase in heart rate was also observed with the administration of umeclidinium/vilanterol. The maximum mean difference in heart rate from placebo after baseline-correction was 8.4 (90% CI: 7.0, 9.8) beats/min and 20.3 (90% CI: 18.9, 21.7) beats/min seen 10 minutes after dosing for umeclidinium/vilanterol 125/25 mcg and umeclidinium/vilanterol 500/100 mcg, respectively.
Umeclidinium 500 mcg was associated with small positive mean differences from placebo in heart rate from 4 to 24 h, inclusive, with a maximum mean difference of 2.1 bpm (90% CI: 0.7, 3.5) at 8 h.
Figure 4 Differences from Placebo (and 90% CIs) in Adjusted Mean Change from Baseline in Heart Rate (bpm) by Time on Day 10 (manually read ECGs)
Additional trials
Studies 200109 and 200110 were 12-week randomized, double-blind, parallel-group studies of umeclidinium 62.5 mcg + fluticasone furoate/vilanterol 100/25 mcg once-daily compared to placebo + fluticasone furoate/vilanterol 100/25 mcg. The primary endpoint was change from baseline in trough (predose) FEV1 at Day 85 (defined as the mean of the FEV1 values obtained at 23 and 24 hours after the previous dose on Day 84).
The results showed that patients treated with umeclidinium 62.5 mcg + fluticasone furoate/vilanterol 100/25 mcg had statistically significant greater mean changes from baseline in trough FEV1 relative to placebo + fluticasone furoate/vilanterol 100/25 mcg (124 mL, 95% CI: 93-154 mL; 122 mL 95% CI: 91-152 mL).
10.3 Pharmacokinetics
The systemic pharmacokinetics of the components of TRELEGY ELLIPTA 100/62.5/25 mcg was assessed in 43 healthy subjects. Four inhalations of fluticasone furoate/umeclidinium/vilanterol 100/62.5/25 mcg were administered as a single dose (see Table 7).
Table 7 Fluticasone Furoate, Umeclidinium and Vilanterol Pharmacokinetic Parameters in Healthy Subjectsa
Fluticasone furoate/umeclidinium/vilanterol 100/62.5/25 mcg single dose (4 inhalations) | Tmax (h) Median (range) | t½ (h) Geometric Mean (CV%) | Cmax (pg/mL) Geometric Mean [95% CI] | AUC(0-t) (pg.h/mL) Geometric Mean (CV%) |
| Fluticasone Furoate 400 mcg | 0.250 (0.05, 2.00) | Not available | 81.07 [72.19, 91.05] | 607.3 (49.9) |
| Umeclidinium 250 mcg | 0.08 (0.05, 0.12) | 2.275 (31.6)b | 539.47 [443.06, 656.86] | 322.5 (45.6) |
| Vilanterol 100 mcg | 0.12 (0.08, 0.17) | 4.804 (65.9)b | 637.53 [580.17, 700.55] | 488.3 (27.5) |
a Pharmacokinetic parameters derived using non-compartmental analysis (NCA)
b Number of subjects for whom parameter is derived = 22 for umeclidinium and 20 for vilanterol
COPD
Population PK analyses for TRELEGY ELLIPTA were conducted using a combined dataset from three phase III studies in 821 COPD subjects, including 413 subjects who received TRELEGY ELLIPTA 100/62.5/25 mcg. Steady state Cmax and AUC0-24 values of fluticasone furoate, umeclidinium and vilanterol following administration of TRELEGY ELLIPTA 100/62.5/25 mcg in one inhaler are presented in Table 8.
Table 8 Fluticasone Furoate, Umeclidinium and Vilanterol Pharmacokinetic Parameters in 413 Subjects with COPDa (Geometric Mean [95% CI])
| Fluticasone furoate/umeclidinium/vilanterol 100/62.5/25 mcg | Cmax (pg/mL) | AUC(0-24) (pg.h/mL) |
| Fluticasone Furoate 100 mcg | 18.7 [18.0, 19.4] | 230 [219, 242] |
| Umeclidinium 62.5 mcg | 59.6 [56.9, 62.4] | 405 [387, 424] |
| Vilanterol 25 mcg | 67.4 [65.0, 70.0] | 362 [348, 377] |
a Pharmacokinetic parameters derived using population pk analysis
Covariate analysis showed higher fluticasone furoate apparent clearance (42%) when comparing fluticasone furoate/vilanterol to fluticasone furoate/umeclidinium/vilanterol; however, this is not considered clinically relevant.
Asthma
The systemic pharmacokinetics of the components of TRELEGY ELLIPTA was assessed in subjects with asthma (1,265 subjects for fluticasone furoate; 634 subjects for umeclidinium; 1,263 subjects for vilanterol) via population PK approach. In these analyses, systemic drug levels (steady-state Cmax and AUC0-24) of fluticasone furoate and vilanterol following fluticasone furoate/umeclidinium/vilanterol (100/62.5/25 mcg and 200/62.5/25 mcg) in one inhaler (triple combination) were within the range of those observed following administration of the dual combination of fluticasone furoate/vilanterol with respect to 100 mcg and 200 mcg fluticasone furoate doses. The systemic exposure of umeclidinium
62.5 mcg following fluticasone furoate/umeclidinium/vilanterol in one inhaler was within the range of those observed following administration of umeclidinium 62.5 mcg as monotherapy.
Steady state Cmax and AUC0-24 values of fluticasone furoate, umeclidinium and vilanterol following administration of TRELEGY ELLIPTA 100/62.5/25 mcg and 200/62.5/25 mcg in one inhaler are presented in Table 9.
Table 9 Summary of Fluticasone Furoate, Umeclidinium and Vilanterol (Cmax and AUC(0-24)) in Subjects with Asthma (Geometric Mean [95% CI])
| Cmax (pg/mL) | AUC(0-24) (pg.h/mL) | |||
|---|---|---|---|---|
| Fluticasone furoate/umeclidinium/vilanterol 100/62.5/25 mcg | ||||
| Fluticasone Furoate 100 mcg | 14.1 (13.5, 14.7) | 225 (214, 236) | ||
| Umeclidinium 62.5 mcg | 35.6 (33.9, 37.3) | 362 (348, 377) | ||
| Vilanterol 25 mcg | 63.0 (59.7, 66.5) | 266 (250, 283) | ||
| Fluticasone furoate/umeclidinium/vilanterol 200/62.5/25 mcg | ||||
| Fluticasone Furoate 200 mcg | 30.6 (29.1, 32.2) | 504 (474, 535) | ||
| Umeclidinium 62.5 mcg | 36.4 (34.2, 38.8) | 363 (349, 378) | ||
| Vilanterol 25 mcg | 62.2 (59.0, 65.6) | 281 (263, 300) | ||
Absorption
Fluticasone Furoate: Following inhaled administration of fluticasone furoate/umeclidinium/vilanterol in healthy subjects, fluticasone furoate Cmax occurred at 15 minutes. The absolute bioavailability of fluticasone furoate when administrated as fluticasone furoate/vilanterol by inhalation was on average 15.2%, primarily due to absorption of the inhaled portion of the dose delivered to the lung, with negligible contribution from oral absorption. Following repeat dosing of inhaled fluticasone furoate/vilanterol, steady state was achieved within 6 days with up to 1.6-fold accumulation.
Umeclidinium: Following inhaled administration of fluticasone furoate/umeclidinium/vilanterol in healthy subjects, umeclidinium Cmax occurred at 5 minutes. The absolute bioavailability of inhaled umeclidinium was on average 13%, with negligible contribution from oral absorption. Following repeat dosing of inhaled umeclidinium, steady state was achieved within 7 to 10 days with 1.5 to 2-fold accumulation.
Vilanterol: Following inhaled administration of fluticasone furoate/umeclidinium/vilanterol in healthy subjects, vilanterol Cmax occurred at 7 minutes. The absolute bioavailability of inhaled vilanterol when administered as fluticasone furoate/vilanterol by inhalation was on average 27%, with negligible contribution from oral absorption. Following repeat dosing of inhaled fluticasone furoate/vilanterol, steady state was achieved within 6 days with up to 1.5-fold accumulation.
Distribution
Fluticasone Furoate: Following intravenous administration to healthy subjects, the mean volume of distribution at steady state was 661 L. The binding of fluticasone furoate to human plasma proteins was high (99.6%).
Umeclidinium: Following intravenous administration to healthy subjects, the mean volume of distribution was 86 L. In vitro plasma protein binding in human plasma was on average 89%.
Vilanterol: Following intravenous administration to healthy volunteers, the mean volume of distribution at steady state was 165 L. In vitro plasma protein binding in human plasma was on average 94%.
Metabolism
Fluticasone Furoate: In vitro studies showed that fluticasone furoate is metabolised principally by CYP3A4 and is a substrate for the P-glycoprotein (P-gp) transporter. Fluticasone furoate is primarily metabolised through hydrolysis of the S-fluoromethyl carbothioate group to metabolites with significantly reduced corticosteroid activity. Systemic exposure to the metabolites is low.
Umeclidinium: In vitro studies showed that umeclidinium is metabolized principally by CYP2D6 and is a substrate for the P-gp transporter. The primary metabolic routes for umeclidinium are oxidative (hydroxylation, O-dealkylation) followed by conjugation (e.g., glucuronidation, etc.), resulting in a range of metabolites with either reduced pharmacological activity or for which the pharmacological activity has not been established. Systemic exposure to the metabolites is low.
Vilanterol: In vitro studies showed that vilanterol was metabolized principally via CYP3A4 and is a substrate for the P-gp transporter. The primary metabolic routes are O-dealkylation to a range of metabolites with significantly reduced beta1-and beta2-agonist activity. Plasma metabolic profiles following oral administration of vilanterol in a human radiolabel study were consistent with high first-pass metabolism. Systemic exposure to the metabolites is low.
Elimination
Fluticasone Furoate: Fluticasone furoate and its metabolites are eliminated primarily in the feces, accounting for approximately 101% and 90% of the orally and intravenously administered dose, respectively. Urinary excretion accounted for approximately 1% and 2% of the orally and intravenously administered doses, respectively. Following repeat-dose inhaled administration, the plasma elimination phase half-life averaged 24 hours.
Umeclidinium: Plasma clearance following intravenous administration was 151 L/hr. Following intravenous administration, approximately 58% of the administered radiolabeled dose (or 73% of the recovered radioactivity) was excreted in feces and 22% of the administered radiolabelled dose (27% of recovered radioactivity) in urine. The excretion of the drug-related material in the feces following intravenous dosing indicated secretion into the bile. Following oral administration to healthy male subjects, total radioactivity was excreted primarily in feces (92% of the administered radiolabelled dose). Less than 1% of the orally administered dose was excreted in urine, suggesting negligible absorption following oral administration. Umeclidinium plasma elimination half-life following inhaled dosing for 10 days averaged 19 hours, with 3% to 4% drug excreted unchanged in urine at steady-state.
Vilanterol: Plasma clearance of vilanterol following intravenous administration was 108 L/hr. Following oral administration of radiolabelled vilanterol, mass balance showed 70% of the radiolabel in urine and 30% in feces. Primary elimination of vilanterol was by metabolism followed by excretion of metabolites in urine and feces. Vilanterol plasma elimination half-life following inhaled dosing for 10 days averaged 11 hours.
Special Populations and Conditions
Pediatrics: The safety and efficacy of TRELEGY ELLIPTA in pediatric patients below 18 years of age have not been established.
Effects on Growth: Inhaled corticosteroids may cause a reduction in growth velocity when administered to children and adolescents. A reduction of growth velocity in children and adolescents may occur as a result of poorly controlled asthma or from use of corticosteroids, including inhaled corticosteroids. The effects of long-term treatment of children and adolescents with inhaled corticosteroids, including fluticasone furoate, on final adult height are not known.
Controlled clinical trials have shown that inhaled corticosteroids may cause a reduction in growth in children. In these trials, the mean reduction in growth velocity was approximately 1 cm/year (range: 0.3 to 1.8 cm/year) and appears to be related to dose and duration of exposure. This effect has been observed in the absence of laboratory evidence of HPA axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in children than some commonly used tests of HPA axis function. The long-term effects of this reduction in growth velocity associated with inhaled corticosteroids, including the impact on final adult height, are unknown. The potential for “catch-up” growth following discontinuation of treatment with inhaled corticosteroids has not been adequately studied.
A randomized, double-blind, parallel-group, multicenter, 1-year, placebo-controlled trial evaluated the effect of once-daily treatment with 110 mcg of fluticasone furoate in the nasal spray formulation on growth velocity assessed by stadiometry. The subjects were 474 pre-pubescent children (girls aged 5 to 7.5 years and boys aged 5 to 8.5 years). Mean growth velocity over the 52-week treatment period was lower in the patients receiving fluticasone furoate nasal spray (5.19 cm/year) compared with placebo (5.46 cm/year). The mean reduction in growth velocity was 0.27 cm/year (95% CI: 0.06 to 0.48) (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Geriatrics: The effects of age on the pharmacokinetics of fluticasone furoate, umeclidinium and vilanterol were evaluated in population pharmacokinetic analyses. No clinically relevant effects requiring dose adjustment were observed for subjects with COPD or asthma.
Sex: In population pharmacokinetic analyses in subjects with COPD or asthma, no clinically relevant differences requiring dose adjustment based on gender were observed in fluticasone furoate, umeclidinium or vilanterol systemic exposure.
Ethnic origin: No clinically relevant differences requiring dose adjustment in COPD or asthma based on race were observed in fluticasone furoate, umeclidinium or vilanterol systemic exposure.
In 113 East Asian subjects with COPD (Japanese and East Asian Heritage), who received fluticasone furoate/umeclidinium/vilanterol 100/62.5/25 mcg from a single inhaler (27% subjects), fluticasone furoate and umeclidinium AUCSS estimates were on average 30% and 33%, respectively, higher compared with Caucasian subjects. However, these higher fluticasone furoate systemic exposures remain below the threshold for fluticasone furoate-induced reduction of serum and urine cortisol and are not considered clinically relevant. Also, these higher umeclidinium systemic exposures are not expected to be clinically relevant with respect to safety in these subjects.
There was no effect of race on pharmacokinetic parameter estimates of vilanterol in subjects with COPD.
In 92 East Asian subjects with asthma (Japanese, East Asian and Southeast Asian heritage) who provided fluticasone furoate/umeclidinium/vilanterol (100/62.5/25 mcg or 200/62.5/25 mcg) population pharmacokinetic data, estimates of vilanterol Cmax at steady state was approximately 3-fold higher than non-East Asian subjects.
There was no effect of race on pharmacokinetics of fluticasone furoate or umeclidinium in subjects with asthma.
Hepatic Insufficiency: Fluticasone furoate/umeclidinium/vilanterol has not been evaluated in subjects with hepatic impairment. However, studies have been conducted with fluticasone furoate/vilanterol and umeclidinium/vilanterol.
The impact of hepatic impairment on the pharmacokinetics of combination doses of fluticasone furoate/vilanterol was evaluated in patients with mild (n=9), moderate (n=9) and severe (n=8) hepatic insufficiency, stratified using the Child-Pugh classification. Subjects with mild or moderate hepatic impairment and healthy control subjects (n=9) received fluticasone furoate/vilanterol 200/25 mcg once daily for 7 days. As a precaution, subjects with severe hepatic impairment received a lower combination dose of fluticasone furoate/vilanterol 100/12.5 mcg once daily for 7 days. There was an increase in fluticasone furoate systemic exposure (up to 3-fold increase in AUC(0-24)) in subjects with mild, moderate, or severe hepatic impairment compared with healthy subjects. No clinically relevant effects on weighted mean serum cortisol were observed in subjects with mild hepatic impairment. In subjects with moderate hepatic impairment, mean serum cortisol (0 to 24 hours) was reduced by 34% compared with healthy subjects. Hepatic impairment had no effect on vilanterol systemic exposure. For patients with moderate or severe hepatic impairment the maximum dose is TRELEGY ELLIPTA 100/62.5/25 mcg (4.2 Recommended Dose and Dosage Adjustment, Hepatic Insufficiency).
The pharmacokinetics of umeclidinium and vilanterol following co-administration have been evaluated in subjects with moderate hepatic impairment (Child-Pugh score of 7-9). There was no evidence of an increase in systemic exposure to either umeclidinium or vilanterol (Cmax and AUC), and no evidence of altered protein binding between subjects with moderate hepatic impairment and healthy volunteers. Umeclidinium has not been evaluated in subjects with severe hepatic impairment.
Renal Insufficiency: Fluticasone furoate/umeclidinium/vilanterol has not been evaluated in subjects with renal impairment. However, studies have been conducted with fluticasone furoate/vilanterol and umeclidinium/vilanterol.
A clinical pharmacology study of fluticasone furoate/vilanterol showed that severe renal impairment (creatinine clearance <30mL/min) did not result in significantly greater exposure to fluticasone furoate or vilanterol compared with healthy subjects.
The pharmacokinetics of umeclidinium and vilanterol following co-administration have been evaluated in subjects with severe renal impairment (creatinine clearance <30 mL/min). Umeclidinium systemic exposure was not significantly increased (10% for AUC) and vilanterol systemic exposure (AUC(0-24)) was 56% higher in subjects with severe renal impairment compared with healthy subjects. There was no evidence of altered protein binding between subjects with severe renal impairment and healthy volunteers.
11 STORAGE, STABILITY AND DISPOSAL
Do not store above 30°C. Store in a dry place away from direct heat or sunlight. If stored in the refrigerator, allow the inhaler to return to room temperature for at least an hour before use.
Keep out of sight and reach of children.
Patients should be instructed to write the date the inhaler should be discarded on the label in the space provided. The date (6 weeks after the date of opening) should be added as soon as the inhaler has been removed from the tray.
TRELEGY ELLIPTA should be safely discarded when the dose counter reads “0” or 6 weeks after it was removed from the foil tray, whichever comes first.
12 SPECIAL HANDLING INSTRUCTIONS
TRELEGY ELLIPTA is packaged in a moisture-protective foil laminate tray with a desiccant sachet and a peelable foil lid. TRELEGY ELLIPTA should be stored inside the unopened moisture-protective foil laminate tray and only removed from the tray immediately before initial use. Once the tray is opened, the desiccant package should be discarded in the household trash out of reach of children and pets. It should not be opened, eaten or inhaled.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Fluticasone Furoate
Proper name: fluticasone furoate
Chemical name: (6α,11β,16α,17α)-6,9-difluoro-17-{[(fluoro-methyl)thio]carbonyl}-11-hydroxy-16-methyl-3-oxoandrosta-1,4-dien-17-yl 2-furancarboxylate
Molecular formula and molecular mass: C27H29F3O6S 538.6
Structural formula:
Physicochemical properties: fluticasone furoate is a white powder. It is practically insoluble in water.
Umeclidinium Bromide
Proper name: umeclidinium bromide
Chemical name: 1-[2-(benzyloxy)ethyl]-4-(hydroxydiphenylmethyl)-1-azoniabicyclo[2.2.2]octane bromide
Molecular formula and molecular mass: C29H34 NO2•Br 508.5
Structural formula:
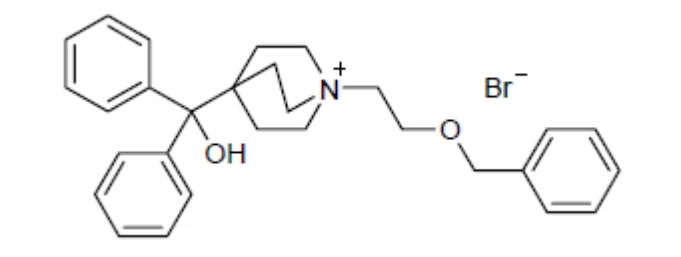
Physicochemical properties: umeclidinium is a white powder. It is slightly soluble in water.
Vilanterol Trifenatate
Proper name: vilanterol trifenatate
Chemical name: triphenylacetic acid-4-{(1R)-2-[(6-{2-[2,6 dicholorobenzyl)oxy]ethoxy}hexyl)amino]-1-
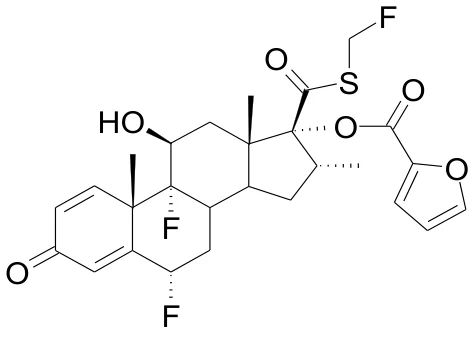
hydroxyethyl}-2-(hydroxymethyl)phenol (1:1)
Molecular formula and molecular mass: C24H33Cl2NO5.C20H16O2 774.8
Structural formula:
OH NH OH O O Cl Cl OH .Ph3CCO2H
Physicochemical properties: vilanterol is a white powder. It is practically insoluble in water.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
COPD
TRELEGY ELLIPTA 100/62.5/25 mcg is a triple combination of fluticasone furoate, an inhaled corticosteroid (ICS), umeclidinium, a long-acting muscarinic antagonist (LAMA) and vilanterol, a long-acting beta2-adrenergic agonist (LABA) for oral inhalation. The efficacy of TRELEGY ELLIPTA in patients with a clinical diagnosis of COPD has been evaluated in two clinical studies: CTT116853 and CTT116855.
The details of the design and patient demographics for these studies are described in Table 10 below.
Table 10 Summary of trial design and patient demographics for clinical trials in COPD
| Study # | Trial design, Route of Administration and Study Duration | Treatment and Dosage | Study Subjects Mean age (Range) Gender (%) | Primary Efficacy Endpoint |
| CTT116853 | 24 week, randomised, double blind, double dummy, parallel group study (with an extension to 52 weeks in a subset of subjects) comparing the efficacy, safety and tolerability of the fixed dose triple combination fluticasone furoate/ umeclidinium/ vilanterol administered once daily in the morning via a dry powder inhaler (ELLIPTA) with budesonide/formoterol (BUD/FOR) administered twice-daily via the Turbuhaler dry powder inhaler | TRELEGY ELLIPTA 100/62.5/25 mcg OD BUD/FOR 400/12 mcg BID | ITT Population (24 weeks) Total: 1,810 64 years (39 - 99) Male: 74% Female: 26% EXT Population (52 weeks) Total: 430 64 years (41-81) Male: 74% Female: 26% | Trough FEV1 at Week 24 and SGRQ Total Score at Week 24 |
| Study # | Trial design, Route of Administration and Study Duration | Treatment and Dosage | Study Subjects Mean age (Range) Gender (%) | Primary Efficacy Endpoint |
| CTT116855 | 52 week, randomised, double blind, 3-arm parallel group study, comparing the efficacy, safety and tolerability of the fixed dose triple combination fluticasone furoate/umeclidinium/ vilanterol with the fixed dose dual combinations of fluticasone furoate/vilanterol (FF/VI) and umeclidinium/ vilanterol (UMEC/VI), all administered once daily in the morning via a dry powder inhaler (ELLIPTA) | TRELEGY ELLIPTA 100/62.5/25 mcg OD FF/VI 100/25 mcg OD UMEC/VI 62.5/25 mcg OD | Total: 10,355 65 years (40-94) Male: 66% Female: 34% | Annual rate of on-treatment moderate/ severe exacerbations |
Study CTT116853
Study CTT116853 was a 24-week active-controlled study in patients with a clinical diagnosis of COPD with an extension up to 52 weeks in a subset of patients. This pivotal study was designed to provide evidence of superior efficacy of TRELEGY ELLIPTA 100/62.5/25 mcg compared with a currently approved ICS/LABA combination indicated for the treatment of patients with moderate to severe COPD with persistent symptoms and a history of exacerbations. The co-primary endpoints were change from baseline in trough forced expiratory volume in one second (FEV1) at Week 24 and change from baseline in St. George's Respiratory Questionnaire (SGRQ) Total Score at Week 24. Secondary efficacy endpoints included: annual rate of moderate or severe COPD exacerbations (on-treatment), change from baseline in Evaluating Respiratory Symptoms in COPD (E-RS: COPD) score and subscale (breathlessness, cough and sputum, and chest symptoms) scores, Transitional Dyspnoea Index (TDI) Focal Score at Week 24, and percentage of days with a Daily Activity Question score of 2 (did more activities than usual) over Weeks 1-24.
A total of 1,810 patients were included in the 24-week active controlled study, and 430 subjects continued up to 52 weeks of treatment. Patients were required to be symptomatic with a COPD Assessment Test (CAT) score ≥10 and on COPD maintenance therapy for at least three months prior to study entry. The mean age was 63.9 years, with 50% of patients aged 65 or over. At screening, the mean post-bronchodilator FEV1 was 45% of predicted and 65% of patients reported a history of moderate/severe exacerbation in the past year. At study entry, the most common COPD medication combinations reported were ICS+LABA+LAMA (28%), ICS+LABA (29%), LAMA+LABA (10%), and LAMA (9%).
TRELEGY ELLIPTA 100/62.5/25 mcg demonstrated a clinically and statistically significant improvement in bronchodilation (as defined by change from baseline trough FEV1 at Week 24; co-primary endpoint) compared with the ICS/LABA administered twice-daily (see Table 11). Lung function improvements with TRELEGY ELLIPTA 100/62.5/25 mcg were evident on the first day of treatment and were maintained over the 24-week treatment period. Over the 24-week treatment period, TRELEGY ELLIPTA 100/62.5/25 mcg produced clinically meaningful improvements from baseline in trough FEV1 at all time points ranging from 118 to 142 mL compared with slight declines observed with the ICS/LABA ranging from -4 to -29 mL. Treatment differences between TRELEGY ELLIPTA 100/62.5/25 mcg and the active comparator in change from baseline in trough FEV1 ranged from 123 to 171 mL and were statistically significant at all time points (p<0.001) (see Figure 5).
TRELEGY ELLIPTA 100/62.5/25 mcg demonstrated a statistically significant improvement compared to the ICS/LABA at Week 24 for Health Related Quality of Life (HRQoL) measured by the St. George’s Respiratory Questionnaire (SGRQ) total score (co-primary endpoint) (see Table 11).
Table 11 Co-primary efficacy endpoints (Study CTT116853)
| TRELEGY ELLIPTA 100/62.5/25 mcg OD (n = 911) | ICS/LABA BID (n = 899) | Comparison with ICS/LABA | ||||||
|---|---|---|---|---|---|---|---|---|
| Treatment Difference (95% CI) p-value | ||||||||
| Trough FEV1 (L) at Week 24, LS mean change from baseline (SE) | 0.142 (0.0083) | -0.029 (0.0085) | 0.171 (0.148, 0.194) p<0.001 | |||||
| SGRQ Total Score at Week 24, LS mean change from baseline (SE) | -6.6 (0.45) | -4.3 (0.46) | -2.2 (-3.5, -1.0) p<0.001 | |||||
| Abbreviations: BID = twice daily; CI = confidence interval; FEV1 = forced expiratory volume in 1 second; L = litres; LS = least squares; mcg = micrograms; n = number in the intent-to-treat population; OD = once daily; SE = standard error; SGRQ = St. George’s Respiratory Questionnaire. | ||||||||
Figure 5 Least Squares Mean Change from Baseline in Trough FEV1 (L) (ITT Population)
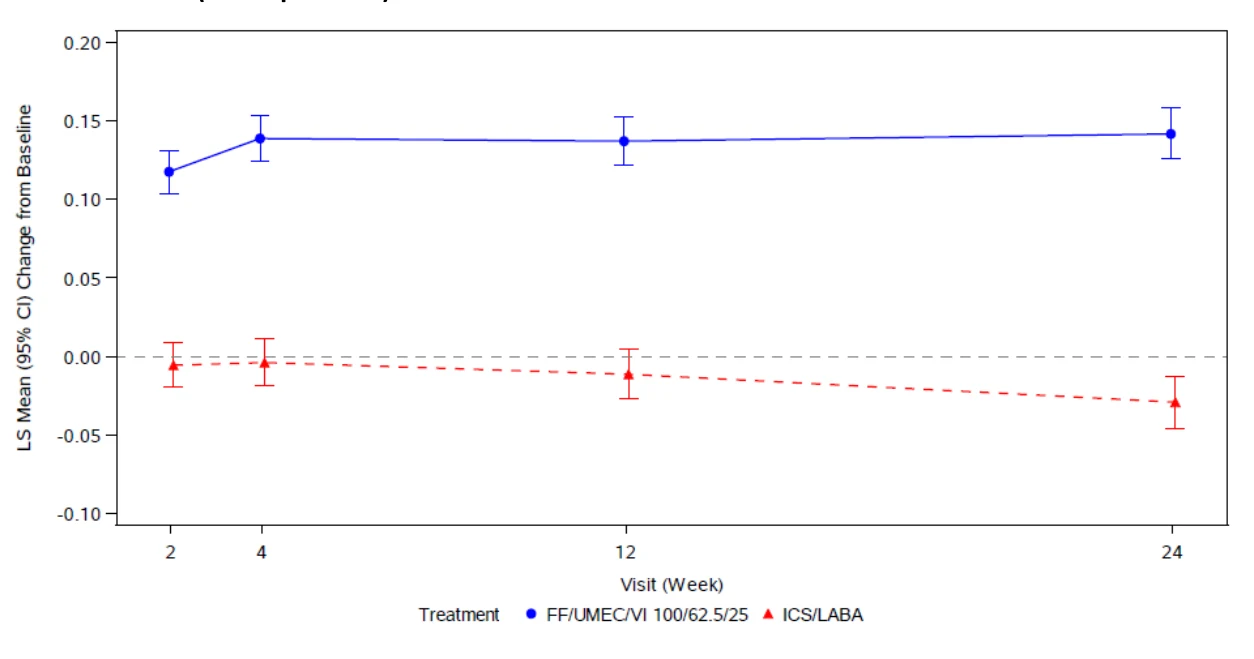
Analysis performed using a repeated measures model with covariates of treatment group, smoking status (screening), geographical region, visit, baseline, and baseline-by-visit and treatment-by-visit interactions
These results were supported by SGRQ responder analysis, CAT score and CAT responder analysis, and also by respiratory symptoms measured using the Evaluating Respiratory Symptoms in COPD (E-RSTM: COPD) score and sub-scale scores over Weeks 21-24, breathlessness measured using the Transitional Dyspnoea Index (TDI) focal score at Week 24, and rescue medication use measured by mean number of occasions per day over Weeks 1-24.
TRELEGY ELLIPTA 100/62.5/25 mcg demonstrated a statistically significant reduction in the annual rate of moderate/severe exacerbations (i.e., requiring treatment with antibiotics or oral/systemic corticosteroids or hospitalization; extrapolated from data up to Week 24) compared with the ICS/LABA.
The results for the extended population (n=430) at 52 weeks for trough FEV1, decrease from baseline in SGRQ Total Score and exacerbation outcomes were consistent with the results up to 24 weeks.
Study CTT116855
Study CTT116855 was a 52-week, active-controlled study evaluating the long-term efficacy of TRELEGY ELLIPTA 100/62.5/25 mcg in patients with COPD with a history of 1 or more moderate or severe exacerbations within the prior 12 months. This pivotal study was designed to provide evidence of superior efficacy of TRELEGY ELLIPTA 100/62.5/25 mcg, compared with a currently approved ICS/LABA combination indicated for the treatment of airflow obstruction in patients with COPD and to reduce exacerbations of COPD, or a currently approved LAMA/LABA combination indicated for the treatment of airflow obstruction in patients with COPD. The primary endpoint was the annual rate of on-treatment moderate/severe exacerbations. Exacerbations were defined as worsening of 2 or more major symptoms (dyspnea, sputum volume, and sputum purulence) or worsening of any 1 major symptom together with any 1 of the following minor symptoms: sore throat, colds (nasal discharge and/or nasal congestion), fever without other cause, and increased cough or wheeze for at least 2 consecutive days. Exacerbations were considered to be of moderate severity if treatment with systemic corticosteroids and/or antibiotics was required and were considered to be severe if resulted in hospitalization or death. Secondary efficacy endpoints included: change from baseline trough FEV1 and change from baseline SGRQ Total Score at Week 52 versus ICS/LABA, time to first on-treatment moderate/severe exacerbation, and annual rate of on-treatment severe exacerbations versus ICS/LABA and versus LAMA/LABA.
A total of 10,355 patients were included in the 52-week active-controlled study. Patients were required to be symptomatic with a CAT score ≥10 and on COPD maintenance therapy for at least three months prior to study entry. The mean age was 65.3 years, with 54% of patients aged 65 or over. At screening, the mean post-bronchodilator FEV1 was 46% of predicted. At study entry, the most common COPD medications were ICS+LAMA+LABA (34%), ICS+LABA (26%), LAMA+LABA (8%), and LAMA (7%).
Treatment with TRELEGY ELLIPTA 100/62.5/25 mcg statistically significantly reduced the on-treatment annual rate of moderate/severe exacerbations by 15% compared with the ICS/LABA and by 25% compared with the LAMA/LABA (see Table 12).
Table 12 Moderate/Severe COPD Exacerbations (Study CTT116855 Primary Endpoint)
| TRELEGY ELLIPTA 100/62.5/25 mcg OD (n = 4,151) | ICS/LABA OD (n = 4,134) | LAMA/LABA OD (n = 2,070) | TRELEGY ELLIPTA vs. ICS/LABA | TRELEGY ELLIPTA vs. LAMA/LABA | ||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Rate of moderate/severe exacerbations per year | 0.91 | 1.07 | 1.21 | |||||||
| Reduction in rate (%) (95% CI) p-value | 15% (10, 20) p<0.001 | 25% (19, 30) p<0.001 | ||||||||
| Abbreviations: ICS/LABA = inhaled corticosteroid/ long-acting beta2-adrenergic agonist; LAMA/LABA = long-acting muscarinic antagonist/ long-acting beta2-adrenergic agonist; CI = Confidence interval; OD = once daily | ||||||||||
These results were supported by lung function analysis (as defined by change from baseline trough FEV1 at Week 52) and SGRQ score analysis compared to ICS/LABA; time to first moderate/severe exacerbation analysis compared to both ICS/LABA and LAMA/LABA; and rate of severe exacerbations (i.e., requiring hospitalization or resulting in death) compared to LAMA/LABA.
Asthma
The efficacy of TRELEGY ELLIPTA 100/62.5/25 mcg and 200/62.5/25 mcg in patients with a clinical diagnosis of asthma has been evaluated in one pivotal clinical study 205715.
The details of the design and patient demographics for study 205715 are described in Table 13 below.
Table 13 Summary of trial design and patient demographics for clinical trials in Asthma
| Study # | Trial design, Route of Administration and Study Duration | Treatment and Dosage | Study Subjects Mean age (Range) Gender (%) | Primary Efficacy Endpoint |
| 205715 | A 24-52 week phase III, multi-centre, randomized, active-controlled, double-blind, parallel group study to evaluate the efficacy, safety and tolerability of the fixed dose triple combination of fluticasone furoate/umeclidinium bromide/vilanterol (FF/UMEC/VI) with the fixed dose dual combination of fluticasone furoate/vilanterol (FF/VI) all administered once daily via a dry powder inhaler (ELLIPTA) in subjects with inadequately controlled asthma | TRELEGY ELLIPTA 100/62.5/25 mcg OD TRELEGY ELLIPTA 200/62.5/25 mcg OD FF/UMEC/VI 100/31.25/25 mcg OD FF/UMEC/VI 200/31.25/25 mcg OD FF/VI 100/25 mcg OD FF/VI 200/25 mcg OD | ITT Population (24– 52 weeks) Total: 2,436 53 years (18 - 88) Male: 38% Female: 62% | Trough FEV1 at Week 24 |
Study 205715
The safety and efficacy of TRELEGY ELLIPTA 100/62.5/25 mcg and 200/62.5/25 mcg were evaluated in 2,436 subjects in a randomized, active-controlled, double-blind, parallel-group confirmatory trial of 24 to 52 weeks’ duration in adult subjects with asthma inadequately controlled on their current treatments of combination therapy (ICS/LABA). The trial evaluated the efficacy of TRELEGY ELLIPTA on lung function, annualized rate of moderate and severe asthma exacerbations, asthma symptom control, and health-related quality of life when compared with fluticasone furoate/vilanterol (FF/VI). The primary endpoint was change from baseline in trough forced expiratory volume in one second (FEV1) at Week 24. The key secondary endpoint was the annualized rate of moderate/severe asthma exacerbation.
This trial had a 5-week run-in/stabilization period described as follows: subjects inadequately controlled [Asthma Control Questionnaire (ACQ-6) ≥1.5] on their current asthma treatment of ICS (greater than fluticasone propionate 250 mcg/day or equivalent) plus LABA entered a 3-week run-in period of treatment with fluticasone propionate/salmeterol 250/50 mcg twice daily. Subjects who remained inadequately controlled (ACQ-6 ≥1.5) after the run-in period were transferred to fluticasone furoate/vilanterol 100/25 mcg once daily for a 2-week stabilization period.
Across all treatment groups, baseline demographics were similar. In the overall population, the demographics were: mean age of 53 years, 62% female, 80% white, 21 years’ mean duration of asthma (range: 1 to 70), 81% who never smoked. The trial did not include current smokers; past smokers had an average smoking history of 4.3 pack-years. In the prior 12 months, 85% of subjects reported having at least one exacerbation that required oral/systemic corticosteroids and/or hospitalization. At study entry, the most common asthma medication combinations reported were ICS+LABA (82%), ICS+LABA+leukotriene receptor antagonists (LTRA) (9%), and ICS+LABA+LAMA (2%).
At screening, the mean prebronchodilator percent predicted FEV1 was 58.5% (SD: 12.8%); the mean percent reversibility was 29.9% (SD: 18.1%), with a mean absolute reversibility of 484 mL (SD: 274 mL), and the mean ACQ-6 score was 2.5 (SD: 0.6).
During the 5-week run-in/stabilization period, subjects had improvements in both lung function (trough FEV1 improvement of 287 mL) and asthma control (mean ACQ-6 score decreased by 0.6). At randomization, the majority of subjects (93%) remained not well controlled (mean ACQ-6 score of 1.9), and the mean prebronchodilator percent predicted FEV1 was 68.2% (SD: 14.8%).
After the 5-week run-in/stabilization period, eligible subjects were randomized to receive once-daily inhalations of TRELEGY ELLIPTA 100/62.5/25 mcg (n = 406), TRELEGY ELLIPTA 200/62.5/25 mcg (n = 408), FF/UMEC/VI 100/31.25/25 mcg (n = 405), FF/UMEC/VI 200/31.25/25 mcg (n = 404), fluticasone furoate/vilanterol 100/25 mcg (n = 407), or fluticasone furoate/vilanterol 200/25 mcg (n = 406). In the evaluation of efficacy, the non-lung function endpoint analyses included prespecified pooled comparisons of TRELEGY ELLIPTA (100/62.5/25 and 200/62.5/25 mcg) with fluticasone furoate/vilanterol (100/25 and 200/25 mcg).
Lung Function: The change from baseline in trough FEV1 at Week 24 (primary efficacy endpoint) showed statistically significant improvements in lung function for both TRELEGY ELLIPTA 100/62.5/25 mcg and TRELEGY ELLIPTA 200/62.5/25 mcg compared with fluticasone furoate/vilanterol 100/25 mcg and fluticasone furoate/vilanterol 200/25 mcg, respectively (Table 14, Figure 6 and Figure 7).
Table 14 Least Squares Mean Change from Baseline in Trough FEV1 at Week 24
| Trough FEV1 (mL) | FF/VI 100/25 mcg (n = 407) | TRELEGY ELLIPTA 100/62.5/25 mcg (n = 406) | FF/VI 200/25 mcg (n = 406) | TRELEGY ELLIPTA 200/62.5/25 mcg (n = 408) |
|---|---|---|---|---|
| Least squares mean | 2,048 | 2,157 | 2,099 | 2,191 |
| Least squares mean change (SE) | 24 (15.7) | 134 (15.5) | 76 (15.6) | 168 (15.5) |
| TRELEGY ELLIPTA 100/62.5/25 mcg vs. FF/VI 100/25 mcg | ||||
| Difference | Reference | 110 | –– | –– |
| 95% CI | 66, 153 | |||
| P value | p<0.001 | |||
| TRELEGY ELLIPTA 200/62.5/25 mcg vs. FF/VI 200/25 mcg | ||||
| Difference | –– | –– | Reference | 92 |
| 95% CI | 49, 135 | |||
| P value | p<0.001 |
CI=confidence interval; FEV1=forced expiratory volume in 1 second; n=number in the intent-to-treat population; SE=standard error; FF/VI = Fluticasone Furoate/Vilanterol
Figure 6 Least Squares Mean Change from Baseline in Trough FEV1 (mL) with TRELEGY ELLIPTA 100/62.5/25 mcg over 24 Weeks of Treatment
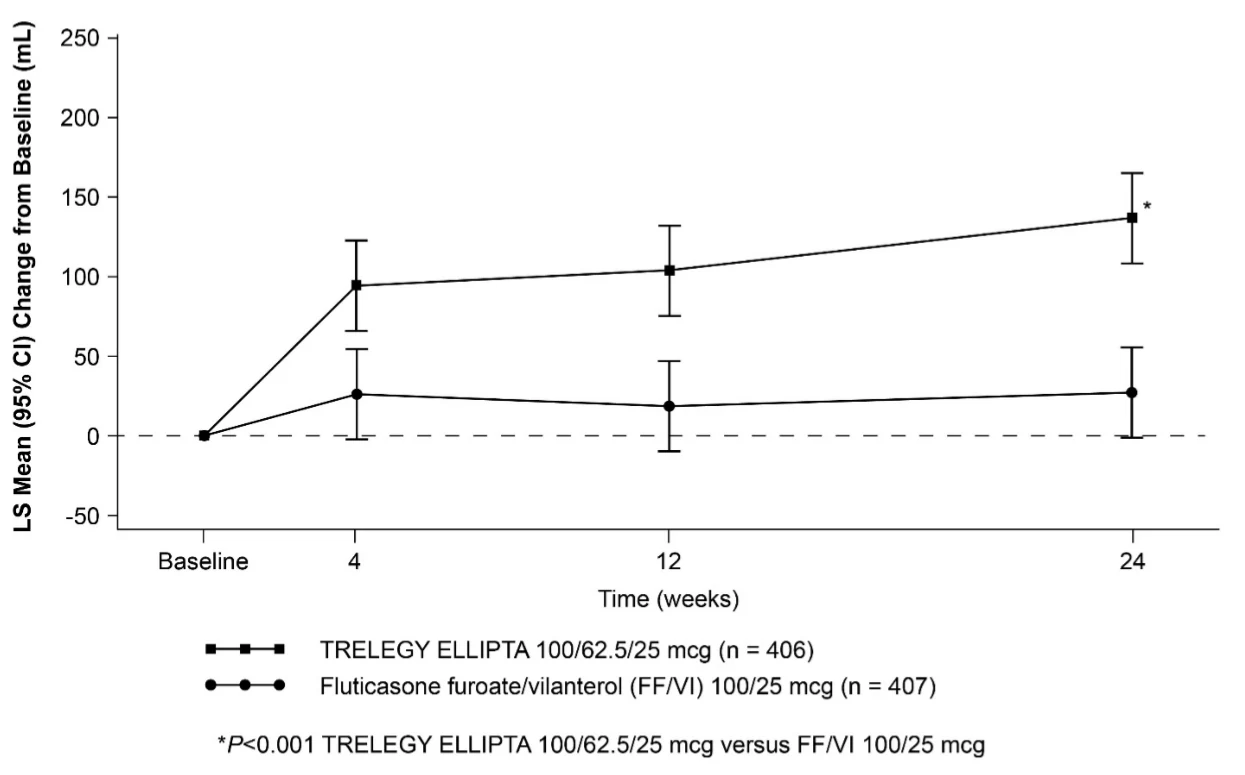
Figure 7 Least Squares Mean Change from Baseline in Trough FEV1 (mL) with TRELEGY ELLIPTA 200/62.5/25 mcg over 24 Weeks of Treatment
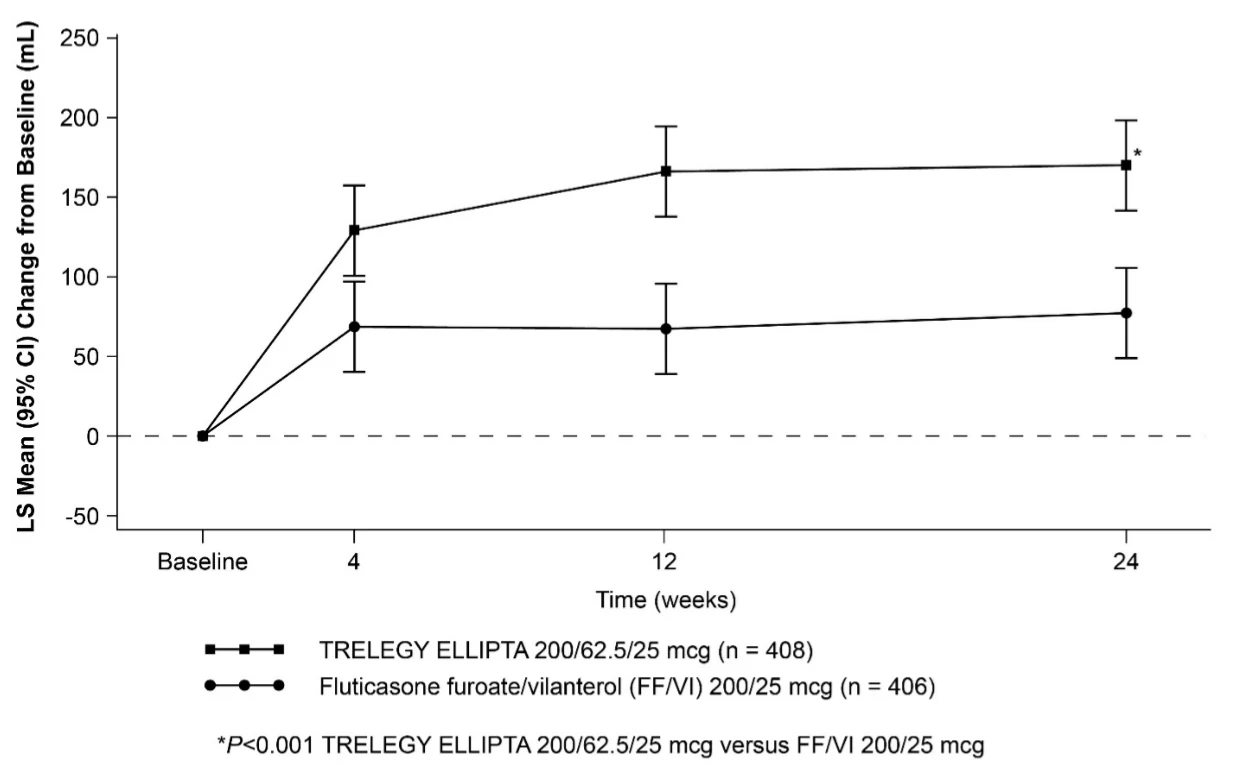
The change from baseline in FEV1 at 3 hours post-dose was supportive of the primary endpoint with improvements for both TRELEGY ELLIPTA 100/62.5/25 mcg and TRELEGY ELLIPTA 200/62.5/25 mcg compared with fluticasone furoate/vilanterol 100/25 mcg and fluticasone furoate/vilanterol 200/25 mcg, respectively.
Exacerbations: Moderate/severe asthma exacerbations were assessed over the 52-week treatment period based on variable treatment duration (from 24 weeks to 52 weeks where 39% of subjects were treated for 36 weeks and 19% of subjects were treated for 52 weeks). A moderate asthma exacerbation was defined as a deterioration in asthma symptoms or lung function, or an increase in rescue bronchodilator use that warranted a temporary change in asthma treatment (e.g., increase in ICS), but did not meet the criteria for severe exacerbation. A severe asthma exacerbation was defined as deterioration of asthma requiring the use of systemic corticosteroid (or at least a doubling of maintenance dose) for at least 3 days, or an inpatient hospitalization or emergency department visit due to asthma that required systemic corticosteroid.
In the pooled analysis, the annualized rate of moderate/severe exacerbations (key secondary endpoint) was lower with TRELEGY ELLIPTA (100/62.5/25 and 200/62.5/25 mcg) compared with fluticasone furoate/vilanterol (100/25 and 200/25 mcg) (13% reduction in rate; 95% CI: -5.2, 28.1).
In descriptive unpooled analyses, the mean annualized rates of moderate/severe exacerbations were 0.68 and 0.55 for TRELEGY ELLIPTA 100/62.5/25 mcg and TRELEGY ELLIPTA 200/62.5/25 mcg, respectively. The mean annualized rates of moderate/severe exacerbations were 0.87 and 0.57 for fluticasone furoate/vilanterol 100/25 mcg and fluticasone furoate/vilanterol 200/25 mcg, respectively.
In addition, severe asthma exacerbations were assessed as an other endpoint. In a descriptive pooled analysis, a difference in the mean annualized rate of severe exacerbations was not observed for TRELEGY ELLIPTA (100/62.5/25 and 200/62.5/25 mcg) compared with fluticasone furoate/vilanterol (100/25 and 200/25 mcg) (2.6% reduction in rate; 95% CI: -26.2, 24.9). In descriptive unpooled analyses, the mean annualized rates of severe exacerbations were 0.41 and 0.23 for TRELEGY ELLIPTA 100/62.5/25 mcg and TRELEGY ELLIPTA 200/62.5/25 mcg, respectively. The mean annualized rates of severe exacerbations were 0.38 and 0.26 for fluticasone furoate/vilanterol 100/25 mcg and fluticasone furoate/vilanterol 200/25 mcg, respectively.
Asthma Control Questionnaire (ACQ): The mean change from baseline in ACQ-7 score at week 24 (pooled analysis was a secondary endpoint) was similar for all treatment groups. In an unpooled descriptive analysis, the ACQ-7 responder rate at Week 24 as an other endpoint was 62% for TRELEGY ELLIPTA 100/62.5/25 mcg compared with 52% for fluticasone furoate/vilanterol 100/25 mcg, and 64% for TRELEGY ELLIPTA 200/62.5/25 mcg compared with 58% for fluticasone furoate/vilanterol 200/25 mcg.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Animal Pharmacology: Pharmacological and toxicological effects seen with fluticasone furoate, umeclidinium or vilanterol in nonclinical studies were those typically associated with glucocorticoids, muscarinic receptor antagonists or beta2-adrenergic receptor agonists. Administration of combined fluticasone furoate, umeclidinium and vilanterol to dogs did not result in any significant new toxicity or any major exacerbation of expected findings associated with fluticasone furoate, umeclidinium or vilanterol alone.
Carcinogenicity: Fluticasone furoate was not genotoxic in a standard battery of studies and was not carcinogenic in lifetime inhalation studies in rats or mice at AUC exposures of 0.6- or 1.3-fold, respectively, those seen in humans given fluticasone furoate 200 mcg.
Umeclidinium was not genotoxic in a standard battery of studies and was not carcinogenic in lifetime inhalation studies in mice or rats at exposures ≥ 20 or ≥ 17-fold the human clinical exposure at umeclidinium 62.5 mcg, based on AUC, respectively.
Genetic toxicity studies indicate vilanterol does not represent a genotoxic hazard to humans. Consistent with findings for other beta2-agonists, in lifetime inhalation studies vilanterol caused proliferative effects in the female rat and mouse reproductive tract and rat pituitary gland. There was no increase in tumour incidence in rats or mice at exposures 0.9 or 22-fold, respectively, the human clinical exposure of vilanterol at 25 micrograms based on AUC.
Reproductive and Developmental Toxicology: Neither fluticasone furoate nor umeclidinium nor vilanterol had any adverse effects on male or female fertility in rats.
Fluticasone furoate was not teratogenic in rats or rabbits, but delayed development in rats and caused abortion in rabbits at maternally toxic inhaled doses. There were no effects on development in rats at exposures 3.0-fold the human clinical exposure at 200 mcg, based on AUC. Fluticasone furoate had no adverse effect on pre- or post-natal development in rats.
Umeclidinium was not teratogenic in rats or rabbits. In a pre- and post-natal study, subcutaneous administration of umeclidinium to rats resulted in lower maternal body weight gain and food consumption and slightly decreased pre-weaning pup body weights in dams given 180 mcg/kg/day dose (approximately 61-fold the human clinical exposure at 62.5 mcg umeclidinium, based on AUC).
Vilanterol was not teratogenic in rats. In inhalation studies in rabbits, vilanterol caused effects similar to those seen with other beta2-agonists (cleft palate, open eyelids, sternebral fusion and limb flexure/malrotation). When given subcutaneously there were no effects at exposures 62-fold the human clinical exposure at 25 mcg, based on AUC. Vilanterol had no adverse effect on pre- or post-natal development in rats.
17 SUPPORTING PRODUCT MONOGRAPHS
BREO ELLIPTA (Dry powder for oral inhalation, 100/25 mcg and 200/25 mcg fluticasone furoate/vilanterol (as trifenatate)), Control No. 213290, Product Monograph, GlaxoSmithKline Inc. (January 07, 2019)
ANORO ELLIPTA (Dry powder for oral inhalation, 62.5/25 mcg umeclidinium (as bromide)/vilanterol (as trifenatate)), Control No. 268656, Product Monograph, GlaxoSmithKline Inc. (March 08, 2023)
INCRUSE ELLIPTA (Dry powder for oral inhalation; 62.5 mcg umeclidinium (as bromide)), Control No. 222505, Product Monograph, GlaxoSmithKline Inc. (September 22, 2020)