


Product Monograph - Intal Inhaler
PRECAUTIONS
Mild throat irritation, coughing and transient bronchospasm may occur. Very rarely, severe bronchospasm associated with a marked fall in pulmonary function has been reported. In such cases treatment should be stopped and should not be reintroduced.
Possible immunologic changes resulting in reactions, such as, polymyositis, pneumonitis and heart failure, urticaria and anaphylaxis have been reported.
Fluorocarbon propellants may be hazardous if they are deliberately abused. Inhalation of high concentrations of aerosol sprays has brought about cardiovascular toxic effects and even death, especially under conditions of hypoxia. However, evidence attests to the relative safety of aerosols when used properly and with adequate ventilation.
Use in Pregnancy
There are no adequate and well controlled studies in pregnant women. However, during clinical use there have been, to date, no reports of adverse effects on the fetus that could be ascribed to the use of sodium cromoglycate. Nevertheless, as with all medications, caution must be exercised during pregnancy. For further information on safety in clinical use, please refer to the section on TERATOGENICITY.
Nursing Mothers
It is not known whether this drug is excreted in human milk; therefore, caution should be exercised when INTAL Inhaler is administered to a nursing woman, and the attending physician must make a benefit/risk assessment in regard to its use in this situation.
ADVERSE REACTIONS
In controlled clinical studies the most frequently reported adverse reactions attributed to sodium cromoglycate treatment were: throat irritation or dryness, bad taste, cough, wheeze and nausea.
Bronchospasm [sometimes severe, associated with precipitous fall in pulmonary function (FEV1)], laryngeal edema (rare), nasal congestion (sometimes severe) and pharyngeal irritation have been reported.
Adverse reactions which occur infrequently and are associated with administration of the drug are: anaphylaxis, angio-edema, dizziness, dysuria and urinary frequency, joint swelling and pain, lacrimation, headache, rash, swollen parotid gland, urticaria, pulmonary infiltrates with eosinophilia, substernal burning and myopathy.
The following adverse reactions have been reported as rare events and it is unclear whether they are attributable to the drug: anaemia, exfoliative dermatitis, haemoptysis, hoarseness, myalgia, nephrosis, periarteritic vasculitis, pericarditis, peripheral neuritis, photodermatitis, sneezing, drowsiness, nasal itching, nasal bleeding, nasal burning, serum sickness, stomach ache, polymyositis, vertigo, and liver disease.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
There have been no reported cases in humans of overdosage of the drug. Symptomatic treatment is suggested should overdosage occur.
DOSAGE AND ADMINISTRATION
Dosage for both Adults and Children over Six Years of Age
INTAL is used on a continuous basis to prevent the symptoms of asthma and has no role in the treatment of acute attacks.
Initial Treatment
Two puffs four times daily at 4-6 hourly intervals. In more severe cases, or during periods of high antigen challenge, the interval between doses may be reduced to 3 hours (i.e., up to 16 puffs daily may be taken).
For protection against bronchospasm induced by exercise, INTAL should be used 15 - 30 minutes beforehand.
Maintenance Therapy
When adequate response has been obtained, the frequency of inhalations may be reduced to 2 puffs every 8 or 12 hours (i.e., 4 or 6 puffs per day). If chest symptoms are troublesome at night, it is important that the final dose be taken, if awakened, during the night.
PATIENTS SHOULD BE WARNED AGAINST SUDDENLY DISCONTINUING THERAPY WHEN SYMPTOMS HAVE BEEN PARTIALLY OR COMPLETELY CONTROLLED BY INTAL.
Concomitant Therapy
Other asthma therapy should be continued until clinical improvement permits a progressive reduction in dosage. However, INTAL alone may prevent symptoms of mild to moderate asthma, especially in children and young adults.
In severe asthma, particularly in older patients, sodium cromoglycate therapy alone is insufficient to prevent symptoms. In a proportion of such cases, significant improvement can be obtained by combining INTAL with corticosteroid therapy, even when inadequate relief is obtained from either drug alone.
In steroid-dependent patients, the addition of sodium cromoglycate to the regimen may permit a slow, progressive and significant reduction in maintenance dose of steroids.
Reduction or Withdrawal of Corticosteroids
The dangers of sudden withdrawal of corticosteroids are well recognized, particularly in steroid-treated patients who have received long-term administration of oral steroids, or injections of adrenocorticotrophic hormone (ACTH).
When the physician attempts to reduce the corticosteroid dosage, it is important that the reduction should be gradual and that close surveillance and frequent examination of the patient is maintained. It should be remembered that the adrenal cortex is suppressed by the administration of oral steroids, and that in both oral steroid and ACTH therapy, the ability of the patient to react to stress is usually impaired. In such patients, acute renal insufficiency and severe asthma can be precipitated by an increase in stress and/or reduction or withdrawal of either steroid or ACTH therapy. In order to identify such a risk in patients who have received long-term steroid therapy, and where substantial reduction or complete withdrawal of corticosteroid is contemplated, it is advisable to assess adrenal and pituitary function.
Method of Reducing Steroid Dosage
The reduction in the daily maintenance dose of steroids should be stepwise at a suggested rate equivalent to about 1% per day (e.g., a maintenance dose of 10 mg prednisolone per day is reduced to 9 mg per day after 1 week). The gradual reduction should be continued until either the patient cannot tolerate a further reduction, or it is found possible to withdraw corticosteroids completely. Note: If troublesome symptoms recur during the period of reduction, the daily dose should be raised immediately. A larger increase in the steroid dose may be essential at times, as a temporary measure, to control a severe relapse induced by antigen challenge, infections or stress. The increased physical or mental activity resulting from subjective improvement can also constitute a stress. When symptoms are brought under control, a progressive reduction may be attempted as before.
Method of Withdrawing ACTH
The same principles apply as discussed above. In practice, either the number of units of ACTH per injection can be reduced, or the interval between injections can be extended (e.g., from 1 per day, to 1 on alternate days, to 1 biweekly).
Withdrawal of INTAL Inhaler Therapy
As the action of sodium cromoglycate is essentially preventive, continuity of therapy is important in patients who have gained benefit. If, for any reason, INTAL is withdrawn, a suggested regimen for withdrawal is to reduce the sodium cromoglycate dosage gradually over a period of one week. It should be borne in mind that symptoms of asthma may recur when the drug is discontinued.
Caution
In cases where INTAL has permitted a reduction in the maintenance dose of steroids, it is recommended that the steroid dose first be restored to at least the pre-sodium cromoglycate level at the commencement of withdrawal of INTAL, followed by slow reduction of the steroid dose to tolerance. This is to avoid risk of acute relapse. It is also recommended that adrenal function be assessed before restoring the pre-sodium cromoglycate steroid dose.
PHARMACEUTICAL INFORMATION
Chemistry
Trade Name: Intal Inhaler
Proper Name: Sodium cromoglycate
Chemical Name: Disodium 5,5'- [(2-hydroxytrimethylene)dioxy]
bis[4-oxo-4H-1-benzopyran-2-carboxylate]
Molecular Formula: C23H14Na2O11
Molecular Weight: 512.34
Structural Formula: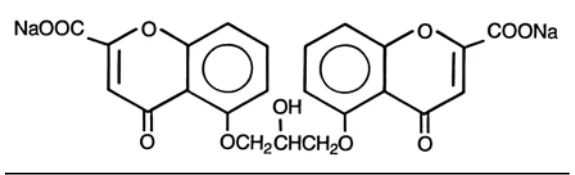
Properties:
Physical form: White or creamy white, hygroscopic powder
Solubility: Soluble in 20 parts of water at 20 C and the resulting solution is neutral.
Insoluble in alcohol (95%) and chloroform.
Composition:
mg/actuation % w/w
Sodium Cromoglycate (micronized) 1.0 1.44
Sorbitan Triolate 0.69 1.0
Dichlorotetraflourethane (BP) 27.06 39.02
Dichlorodiflouromethane (BP) 40.59 58.53
Stability and Storage Recommendations:
Store at room temperature.
Contents under pressure.
Do not place in hot water or near radiators, stoves or other sources of heat. Do not puncture or incinerate container or store at temperatures over 30 C.
AVAILABILITY OF DOSAGE FORM
Intal Inhaler is supplied as a 10 mL pressurized aerosol container delivering 200 metered inhalations. The aerosol contains micronized sodium cromoglycate and sorbitan trioleate as an excipient with dichlorotetrafluoroethane and dichlorodifluoromethane as propellants.
Each actuation delivers 1 mg sodium cromoglycate.
INFORMATION FOR THE CONSUMER
INTAL Inhaler
Sodium cromoglycate inhalation aerosol
Asthma prophylaxis
Preventive Medication:
Sodium cromoglycate works to prevent asthmatic attacks. TO GET THE FULL BENEFIT FROM SODIUM CROMOGLYCATE IT SHOULD BE USED REGULARLY ACCORDING TO YOUR DOCTOR'S INSTRUCTIONS. During the time you are following the regimen, keep a record of the incidence and severity of any asthmatic attacks or symptoms - loss of sleep, wheezing, coughing etc. Your doctor may have provided you with a diary in which to do this. At the end of the month, or other period of time your doctor has designated, this diary can be invaluable in evaluating your sodium cromoglycate regimen. Your doctor will want to know as much as he can about the effect of sodium cromoglycate on the patient's symptoms. You will want to know, too, IF YOU OR YOUR CHILD IS ONE OF THE INDIVIDUALS THIS MEDICINE HELPS. IT CAN BRING A BIG CHANGE FOR THE BETTER IN YOUR LIFE. TAKE THE MEDICINE FOR AT LEAST ONE FULL MONTH TO RECEIVE THE BEST RESULTS AND IT WILL HAVE TO BE TAKEN MONTH AFTER MONTH FOR AS LONG AS YOUR DOCTOR FEELS IS NECESSARY.
Sodium cromoglycate is a preventive medication. It doesn't work immediately so you should continue taking your other medications until your doctor advises otherwise. Do not discontinue use or miss taking the recommended doses without your doctor's approval.
Instructions for Use
To obtain maximum benefit, you must use Intal Inhaler correctly to allow the medication to reach deeply into the lungs. Before using your Intal Inhaler, please read this leaflet, and follow the instructions carefully.
Usual Dosage: Adults and Children over six years - 2 inhalations 4 times daily (e.g. - 2 inhalations on rising; 2 at noon; 2 at 6:00 p.m.; and 2 at bedtime). The number of inhalations and the frequency of use of the inhaler will be determined by your physician. For protection against bronchospasm induced by exercise INTAL should be taken 15 - 30 minutes beforehand.
Important: Do not stop usage or change dosage without consulting your physician. Wash the unit regularly to keep the plastic outlet in the mouthpiece free from powder build-up.
Caution: The canister is pressurized. Do not attempt to puncture it, or dispose of it by burning, even when empty.
Storage: Store at room temperature in a dry location. Keep the cap on when not is use.
IMPORTANT: HOW TO GET THE BEST OUT OF YOUR INHALER
Follow instructions. Keep the unit clean.
Wash the unit twice a week.
- 1) Shake the unit well. Remove the blue cover from the mouthpiece. Ensure that the canister is properly inserted into the inhaler unit.
- 2) Holding the inhaler well away from your mouth, breathe out gently (but not fully). To avoid condensation and blockage of the device, DO NOT breathe out through the mouthpiece.
- 3) Place the mouthpiece in your mouth over your tongue and close your lips around it. Tilt your head well back. Breathe in slowly and deeply through the mouthpiece and, at the same time, press the top of the metal canister down firmly to deliver the Intal. Note: It is essential that the canister is pressed while you are breathing in so that you will get the correct amount of the drug.
- 4) Remove the inhaler from your mouth. Important: Hold your breath for as long as is comfortable (several seconds) to allow the medication to spread through your lungs.
- 5) Wait one minute. Repeat steps 2, 3 and 4. After use, replace the cover on the mouthpiece.
Cleaning:
Important: Keep the plastic body clean to prevent build-up of spare powder. Remove the metal canister and wash the plastic body in warm water at least twice a week. Leave to dry in a warm place overnight. No harm will come from washing the mouthpiece every day.
Note:
Check your technique in front of a mirror from time to time. If you see the white mist escaping into the air, you may not have your lips properly closed around the mouthpiece. Alternatively, you may not be breathing in as you press the canister.
Helpful Hints:
Before using the inhaler for the first time - or if it hasn't been used for a while - give the inhaler one press to test it. For parents: Children may need some help to use the Intal Inhaler correctly. You can help by practising pressing the canister just after the child has started to breathe in.
Each metered inhalation contains sodium cromoglycate micronized 1mg.
LIVING A FULL LIFE WITH ASTHMA
This information sheet will tell you more about asthma and how to deal with it.
What is asthma?
You already know from experience some of the important things about asthma. When you or your child has an attack, breathing becomes very difficult. You also know that, between attacks, you or your child has no problem breathing. So, you know the real problem in having asthma is the "attack". To live more comfortably, you must reduce the number of attacks, stop the attack in progress or reduce the severity of the attack.
What happens during an asthma attack?
An asthma attack does two things to the breathing system. First, it constricts the muscles that control the air passages. These muscles which are wrapped around the outside of the air passages go into spasm which tightens and narrows the air passages. This makes it difficult for air to get in and even more difficult for it to be expelled.
The inside of air passages also is affected by an asthma attack. The inside swells and secretes more mucus than normally, and this mucus interferes with breathing.
What Causes These Attacks?
- 1. Allergy producing substances (ragweed, pollen, dust, some foods and medicines, etc.); 2. Respiratory infections (colds, flu, etc.);
- 3. Strenuous exercise;
- 4. Sudden changes in temperature and/or humidity, (e.g. exposure to cold air); 5. Irritants (chlorine, perfume, etc.);
- 6. Emotional stress (difficult situations at home, school, work).
Relief Measures
Since there is no medicine a patient can take that will cure asthma (that is, end the asthmatic condition forever), relief must concentrate on the prevention of attacks and lessening their severity if they do occur.
Prevention is the key and can be accomplished partially by avoiding the specific triggers of the attack in the individual cases. Try to identify the substances that may cause the attacks you are concerned about - substances such as foods, dust, animal dander, etc. Some measures in this area may be very difficult for children. It may be necessary to find a new home for a family pet or remove a favorite stuffed toy. Even though such steps are unpleasant they may be important and necessary. Pay particular attention to the asthmatic's bedroom: no feather pillows, mattresses or quilts. If a specific food seems to cause problems, eliminate it from the diet. Air conditioning the home reduces the amount of airborne irritants and electrostatic filters, or the newer micropore (HEPA) filters, if practical, may help too. Be careful of certain medicines. Aspirin produces asthmatic reactions in some people and should be avoided if this occurs.
Other Do's and Don'ts - Anyone subject to asthmatic attacks should follow a sensible health promoting lifestyle that includes good nutrition, adequate rest, exercise and these do's and don'ts:
- 1. Don't smoke. Avoid being in the same room with smokers.
- 2. Avoid fresh paint.
- 3. Avoid sudden changes in temperature. Don't go in and out of extremely cool air-conditioned buildings during hot weather.
- 4. Stay home in extremely cold weather, if possible.
- 5. Stay away from people with colds and flu.
- 6. Try not to become involved in emotionally upsetting situations.
- 7. Get plenty of liquid in your daily diet - six to eight glasses.
- 8. Don't overdo it - but do plan regular exercise, especially the kind that helps develop lung capacity.
- 9. Don't take any medicine without telling your doctor.
- 10. Do take all the medication prescribed by your doctor exactly according to his directions. 11. Avoid sleeping pills or sedatives, even if asthma keeps you awake. Prop yourself up with extra pillows until your asthma medication takes effect.
- 12. Avoid inhaling insecticides, deodorants, cleaning fluids, chlorine vapor etc.
PHARMACOLOGY
In vivo Studies in Animals:
The principal effect of sodium cromoglycate is its specific ability to prevent disruption of sensitized cells and thus to inhibit the release of the mediators of anaphylaxis initiated by the interaction of antigen with reagin-type antibodies.
The compound inhibited the passive cutaneous anaphylactic (PCA) reactions in monkeys (Macaca speciosa) sensitized with human reaginic serum when the compound was given intradermally with the antigen. It did not affect the skin reactions to intradermal histamine, 5-hydroxytryptamine or bradykinin. Antigen-induced bronchoconstriction in anaesthetized marmosets (Hapale jacchus) sensitized intravenously with human reaginic serum was substantially reduced by sodium cromoglycate compared with untreated controls.
Homologous PCA reactions with reagin-like antibody in rats using egg albumin/B pertussis and Nippostrongylus brasiliensis sensitized systems showed complete inhibition in the presence of the compound. At cellular level it could be shown that sodium cromoglycate, intravenously, markedly inhibited the rupture of sensitized rat mast cells from subcutaneous connective tissue. Although the drug inhibited PCA reaction, it failed to affect the skin lesions induced by compound 48/80, a potent histamine releaser.
In contrast homologous PCA reactions with precipitating antibody in guinea pigs were unaffected, as were aerosol or intravenous antigen-induced bronchospasm, and the release of histamine and slow-reacting substance (SRS-A) from actively or passively sensitized guinea pig lung in vitro.
Other Experiments
The release of histamine and SRS-A from portions of fresh human lung passively sensitized with human reaginic serum was measured after exposure to specific antigens in vitro. Inhibition with sodium cromoglycate was found over a narrow range of concentrations.
Weighed portions of passively sensitized human lung were "shocked" in an organ bath containing an unsensitized human bronchial chain which contracted in response to the liberated spasmogens. Reproducible contractions were obtained by using fresh pieces of sensitized lung tissue of the same weight. Sodium cromoglycate caused a significant (40%) reduction in contraction compared with the previous control responses.
A further series of experiments, using the isolated ileum of the guinea pig, confirmed that sodium cromoglycate has no antagonizing action against the following spasmogens: histamine, serotonin (5-HT), acetylcholine, nicotine, substance P, bradykinin, or SRS-A.
Sodium cromoglycate has no direct action in human bronchial chain in vitro nor did it antagonize the response to histamine, SRS-A, acetylcholine or prostaglandin F2.
These observations indicate that sodium cromoglycate interferes with the release of spasmogens in some way following the union of antigen and reaginic antibody but does not directly antagonize these spasmogens.
THESE STUDIES EMPHASIZE THAT SODIUM CROMOGLYCATE IS MOST EFFECTIVE WHEN GIVEN PRIOR TO ANTIGEN CHALLENGE.
Sodium cromoglycate is neither a bronchodilator nor an anti-inflammatory agent and has few general pharmacological effects. Its action is distinct from that of corticosteroids in that it appears to inhibit specifically the anaphylactic process initiated by reaginic antibody/antigen reactions.
Large doses of sodium cromoglycate had only weak, inconsistent effects on the cardiovascular and respiratory systems of monkey, pig, cat, guinea pig and rat.
In conscious and anaesthetized dogs, the drug activated chemoreceptors originating in the pulmonary and coronary circulations, mediated by the vagi, producing bradycardia, hypotension, bradypnoea and, sometimes, apnoea.
In the anaesthetized marmoset, sodium cromoglycate caused a rise in blood pressure and heart rate due to stimulation of post-ganglionic sympathetic fibres.
The compound showed no significant effect in several anti-inflammatory tests.
Other experiments showed that the drug does not affect steroid metabolism as indicated by plasma corticosterone and adrenal ascorbic acid levels.
In experiments on isolated frog oesophagus and human bronchial epithelium in vitro and cat trachea in vivo, sodium cromoglycate was used in high concentrations. There was no evidence that the compound interfered with pulmonary clearance. Further work on this aspect of the drug is in progress.
Absorption, Distribution and Excretion
The metabolism and tissue distribution of sodium cromoglycate has been studied in mouse, rat, guinea pig, rabbit, cat, dog, monkey (Macaca speciosa) and man. Sodium cromoglycate, labelled with a radioactive isotope, tritium (3H) has been used for the animal experiments and chemical and spectrofluorimetric methods of estimation for the experiments in man.
- a)
Inhalation Studies
Tritiated sodium cromoglycate has been introduced as a fine powder aerosol into the lungs of rats, rabbits and monkeys. All animals showed rapid clearance of the drug from the lungs, 50% being absorbed in 20 minutes and 98% after 24 hours. The drug is taken up by the liver and kidneys and excreted unchanged via the bile and urine.
Human volunteers who inhaled the drug as powdered aerosol (INTAL) showed a peak plasma level at 10 minutes. This peak was followed by a fall in concentration similar to that demonstrated in the animal experiments. After inhalation, 3 to 5% of the administered dose was excreted in the urine over 6 hours. Assuming a similar biliary excretion, this would indicate that approximately 10% of the administered dose was absorbed.
- b)
Other Routes of Administration
Intravenous and intramuscular administration produces a rapid clearance of the compound from the plasma and a general distribution throughout the tissues followed by rapid excretion unchanged via the kidneys and in the bile. Intramuscular administration resulted in rapid absorption and excretion of a similar pattern to that following intravenous injection.
No tissue accumulation could be detected in the rat and dog after repeated intramuscular injections, the compound being excreted in the urine and bile. In the monkey, 6 hours after intravenous administration 80-90% of the total dose could be accounted for by renal and biliary excretion. At this stage, there is a general distribution of the compound throughout the tissues with higher concentration in the liver and kidney.
In man, oral administration of sodium cromoglycate was followed by a low rate of urinary excretion. The mean urinary excretion of the administered dose over 24 hours was only 0.5%. This indicates that little of the compound is absorbed from the gastrointestinal tract.
TOXICOLOGY
Acute Toxicity
Sodium cromoglycate was administered to a wide variety of animals by the intraperitoneal or the intravenous route. These animals included mice, rats (including newborn and suckling rats), guinea pigs, rabbits, hamsters and monkeys. In most cases, the LD50 was in the region of 4000 mg/kg and in all tests it was above 2000 mg/kg.
Subacute and Chronic Toxicity:
Subcutaneous Injection -- 90-Day Tests in Rats
In one test, groups of 12 rats of each sex were injected daily for 90 days with subcutaneous doses of 30, 78 and 198 mg sodium cromoglycate (tetrahydrate) per kg. At the two higher dose levels, some rats showed haemorrhage at the injection site and some showed renal tubular damage. The only other indications of toxic effects were in the higher dose male rats where the growth rates were depressed and the mean relative weights of the hearts and adrenals were significantly increased. These effects were probably secondary to the renal damage, which was most severe in this group. No effects were detected in the group dosed at 30 mg/kg.
Intravenous Injection -- 180-Day Tests in Monkeys
In this test, groups of 4 male and 4 female Rhesus monkeys were given daily intravenous injections of sodium cromoglycate for 180 days at the following dose levels: 2, 10 and 50 mg/kg. No compound-induced effects were observed.
Proliferative Arteriopathy in Macaque Monkeys
A previously unreported proliferative arterial lesion has been found in some treated and untreated control Macaque monkeys in four out of seven toxicity studies, with sodium cromoglycate. In these four studies, the proliferative arterial lesion occurred predominantly in the kidneys but was also found in other organs. An increased incidence of the lesion in the drug treated group occurred in one of these Macaque monkey studies. Subsequently, the condition has been seen in other laboratories where sodium cromoglycate had not been used.
Proliferative Arteritis in Macaque Monkey in Sodium Cromoglycate Studies
| ROUTE | DURATION | OVERALL | CONTROL | TREATED |
| Inhalation | 3 months | 0 in 18 | 0 in 6 | 0 in 12 |
| Inhalation | 4 months | 5 in 30 | 1 in 18 | 4 in 12 |
| Inhalation | 4 months | 2 in 45 | 1 in 18 | 1 in 27 |
| Inhalation | 3 months | 1 in 25 | 0 in 17 | 1 in 8 |
| I.V. | acute (7 days) | 0 in 16 | none | 0 in 16 |
| I.V. | acute (7 days) | 1 in 8 | 0 in 2 | 1 in 6 |
| I.V. | 6 months | 0 in 30 | 0 in 6 | 0 in 24 |
| TOTAL | 9 in 172 | 2 in 67 | 7 in 105 |
The lesion has not been seen in chronic primate studies utilizing baboons or squirrel monkey treated for six months or longer with sodium cromoglycate or in toxicity studies in rodents.
It is inferred that the lesion may reflect a spontaneous disease of Macaque monkeys. The possibility that the increased incidence of the lesion in treated monkeys is due to the administration of sodium cromoglycate can neither be affirmed or refuted.
Teratogenicity
In tests in rats, no fetal abnormalities were detected following daily subcutaneous injection of sodium cromoglycate at 90 mg/kg throughout pregnancy with or without the addition of 0.05 mg isoproterenol sulphate, these levels of each drug being sufficient to produce evidence of maternal toxicity. Even at a substantially higher dose level (185 mg/kg sodium cromoglycate alone) only one significant deformity (a shortened humerus) was seen in over 270 fetuses examined. Dosing at this level throughout the suckling period had no adverse effects on the young. Treatment of the males at 200 mg/kg for 85 days prior to mating did not affect their fertility.
In mice, daily subcutaneous doses of up to 540 mg/kg sodium cromoglycate given during pregnancy, caused no fetal malformations.
In rabbits, no teratogenic effect was detected when 250 mg/kg sodium cromoglycate alone was given daily for the first 24 days of pregnancy by the intravenous route. At twice this dose, limb flexures were seen in 2 partially resorbed fetus, but all 124 full term fetuses produced were normal. Both these dose levels were sufficient to produce substantial tubular degeneration in the maternal kidney.
Administration of subtoxic doses of sodium cromoglycate, either subcutaneously or intravenously to laboratory animals, did not affect their reproductive performance and no teratogenic effect was observed.
Safety in Pregnancy
A ten-year study was completed in Sri Lanka to test the safety of sodium cromoglycate in pregnancy. Two hundred and ninety-six pregnant asthmatic women 18 to 44 years of age were maintained on 20 mg of sodium cromoglycate, taken by a SPINHALER 2 to 3 times a day during part or throughout the pregnancy. Two hundred and ninety-two of the pregnancies ended in the birth of a normal child whilst 4 infants (1.35%) had malformations. One example each was seen of club foot, non fused septum, harelip without cleft palate and patent ductus arteriosus.
Information on the incidence of congenital malformations within the Sri Lankan population is not available. Epidemiological studies suggest that the incidence of abnormalities is 2 to 3% for the entire human population.
Cytotoxicity
The effects of sodium cromoglycate were studied at the cellular level. Various types of cells were incubated in different concentrations of the drug for several days. No effects were observed at concentrations up to and including 1000 mg/L upon the following:
migration characteristics of guinea-pig macrophages;
morphology of chick embryo fibroblasts;
morphology of human epithelial cells from a cell line; and
ciliary activity of samples of human ciliated epithelium.
The tests on human respiratory epithelium were included to detect potential interference with pulmonary clearance mechanisms.
Effects of Immune Systems
The precise way in which sodium cromoglycate interferes with the release of spasmogens is not yet clear. The effect of the drug was studied on those antibody systems concerned with immunity. In this context no effect was observed on:
various antibody neutralizing or agglutinating systems;
development of active immunity or antibody production; and
protection conferred by passive or active immunity.
No effect was found on the following virus/antibody neutralizing systems in vitro:
influenza A, polio type II with human or rabbit antisera;
vaccinia with rabbit antisera; and
herpes simplex with human antisera.
No effects were observed on the LD50 in mice of mouse adapted polio virus nor in their protection by Salk vaccine.
No effect was found on the neutralization of Clostridium welchii type A- toxin by specific antiserum, nor on the cytotoxic behaviour of rabbit anti-HeLa serum on HeLa cells in vitro.
AEROSOL STUDIES
(a) 12-Week Study in the Rat
In order to ascertain whether there was any toxicological interaction between the sodium cromoglycate and fluorocarbon system, a 12 -week rat study has been carried out with the proposed aerosol formulation. Three treatment groups were exposed for different lengths of time (1, 2 and 4 hours per day) to the same aerosol concentration, and exposure levels were estimated to be some 6, 15 and 30 mg/kg/day.
There were no mortalities, no obvious signs of toxicity, no significant changes in organ weights, no treatment-related changes in haematology or blood biochemistry and no histopathological changes related to sodium cromoglycate observed in the study. There were some changes in alveolar macrophages in some of the groups, but these were minimal and considered to be related to the Span surfactant component of the formulation.
In order to assess the absorption of sodium cromoglycate in this study, radioactive (tritiated) sodium cromoglycate formulated in a similar manner in a pressurized aerosol, was administered to rats, using the same methodology. The amount of sodium cromoglycate available for pulmonary absorption was assessed by measuring the amount of radioactivity in the lungs at various times after exposure and applying a pharmacokinetic model to calculate the amount of compound removed from the lungs during the exposure period. Extrapolation from the values observed in the radioactive study to the toxicity study, and making allowance for the different durations of exposure, showed good agreement with the calculated values of total animal exposure of 6, 15 and 30 mg/kg/day. These doses represent some 40, 100 and 200 times the anticipated human daily dose (2 x l mg qid). However, this does not give an indication of how much of the material is deposited in the lungs. Extrapolation of lung deposition values to the toxicity study would give lung burdens of 0.04 mg/kg body weight/h for males and 0.l7 mg/kg body weight/h for females. Comparison with the human situation where the recommended daily dose is likely to be 8 mg (0.13 mg/kg/day) and assuming that 10% of the human dose is deposited in and absorbed from the lungs (i.e., a greater proportion than in the rat studies) indicates that the rat lung burdens represent between three (males, low dose group) and 60 (females, high dose group) times the maximum human lung burdens.
(b) 26-Week Study in the Dog
A further study of 26-weeks duration has also been carried out in the Beagle dog using the same formulation. In this study, the sodium cromoglycate was administered directly to the respiratory tract at three different dose levels of either 1, 2 or 4 doses per kg body weight, each dose containing 1 mg of sodium cromoglycate.
There were no mortalities, no obvious signs of toxicity, no changes in the mechanical functions of the lung or arterial blood gas values, no changes in haematological or blood chemistry values, no variations in the constituents of urine, no organ weight changes and no histopathological changes that could be attributed to treatment with the sodium cromoglycate formulation.
In order to assess the degree of pulmonary deposition of the administered aerosol, an additional study with four beagle dogs was carried out. In this study, using the same equipment and methodology as in the 26-week study, the dogs were given radioactive doses (tritiated) of sodium cromoglycate to the respiratory tract at the same time that a radioactive (14C) dose of sodium cromoglycate was given as an intravenous infusion.
From this study, assessment of the retained tritiated dose could be extrapolated from the observed changes in plasma concentration with time, and from the observed excretion pattern of the two radioactive labels. The results from this study showed that the estimated pulmonary dose was approximately 9% of the administered dose.
Extrapolation from the values observed in the radioactive study shows that the lowest dose given to the dogs was equivalent to 0.09 mg/kg/day, the medium dose was 0.18 mg/kg/day and the high dose was 0.36 mg/kg/day.
The recommended human daily dose is 2 x 1 mg qid which is equivalent to 0.13 mg/kg/day. As the dose deposited in the human lung is likely to be in the order of only 10% of the administered dose then, from this study, we have a 7-, 14- and 28-fold safety margin.
A study has been conducted in volunteers using the aerosol and it has been shown that absorption amounted to between 2 and 10% of the dose.
CLINICAL SAFETY DATA
The recommended dose per day will be 2 x 1 mg puffs of sodium cromoglycate four times per day, representing a total dose significantly less than is currently used in therapy from the dry powder formulation.
The major constituents in the propellant formulation are dichlorotetrafluoroethane BP (propellant 114) and dichlorodifluoromethane BP (propellant 12). These propellants have been in clinical use for a number of years in formulations supporting the administration of a variety of agents used in the therapy of respiratory disease and have proved acceptable from a safety point of view. The doses used have been of the same order as that currently proposed for the sodium cromoglycate formulation.
Undoubtedly in the therapy of respiratory disease, particularly bronchial asthma, in addition to the powder formulation of sodium cromoglycate, a variety of other agents (particularly bronchodilators) have been concurrently administered from formulations containing propellant 12 and propellant 114.
CONCLUSION
The preclinical data, together with the experience from use in the clinic over a long period of time, of both sodium cromoglycate and the fluorocarbon propellants, have demonstrated that both of these components are acceptable in terms of safety in use. By the nature of the therapy of respiratory disease, a large population of patients have already been subjected to both components concurrently without apparent hazard. The components have been shown to exhibit no toxicological interaction.
SELECTED BIBLIOGRAPHY
- 1. Altounyan REC. Review of the clinical activity and modes of action of sodium cromoglycate. In the mast cell: its role in health and disease. Edited by Pepys J and Edwards AM. London: Pitman Medical 1979;199-216.
- 2. Amlie P, Leegaard J, Lier P, Wefring K. Comparison of sodium cromoglycate pressurised aerosol and powder in the treatment of asthma. Mod Probl Paediat 1982;21:113-7.
- 3. Ashton MJ, Clark B, Jones KM, Moss GF, Neale MG, Ritchie JT. The absorption, metabolism and excretion of disodium cromoglycate in nine animal species. Toxicol Appl Pharmacol 1973;26:319-28.
- 4. Balfour-Lynn L, Tooley M, Godgrey S. Relationship of exercise-induced asthma to clinical asthma in childhood. Arch Dis Child 1981;56:450-4.
- 5. Bar-Yishay E, Gur I, Levy M, Volozni D, Godfrey S. Duration of action of sodium cromoglycate on exercise induced asthma: comparison of two formulations. Arch Dis Child 1983;58(8):624-7.
- 6. Beach JE, Blair AMJN, Clarke AJ, Bonfield CT. Cromolyn sodium toxicity studies in primates. Toxicol Appl Pharmacol 1981;57(3):367-400.
- 7.
Blumenthal MM et al. Cromolyn in extrinsic and intrinsic asthma. J Allergy Clin Immunol
1973;52:105-14.
- 8. Breslin FJ, McFadden ER, Ingram RH. The effects of cromolyn sodium on the airway response to hyperpnea and cold air in asthma. Am Rev Res Dis 1980;122(1):11-16.
- 9. Brompton Hospital/Medical Research Council. Long-term study of disodium cromoglycate in treatment of severe extrinsic or intrinsic asthma in adults. Br Med J 1972;4:383-8.
- 10. Cockcroft DW, Murdock KY. Comparative effects of inhaled salbutamol, sodium cromoglycate, and beclomethasone dipropionate on allergen-induced early asthmatic responses, late asthmatic responses, and increased bronchial responsiveness to histamine. J Allergy Clin Immunol 1987;79(5):734-40.
- 11. Cox JSG. Disodium cromoglycate (FPL 670) ('Intal'): A specific inhibitor of reaginic antibody mechanisms. Nature 1967;216:1328-9.
- 12. Cox JSG. Review of chemistry pharmacology, toxicity, metabolism specific side-effects, anti-allergic properties in vitro and in vivo of disodium cromoglycate. Edited by Pepys J and Frankland AW. Disodium cromoglycate in allergic airways disease. London: Butterworths 1970;13-25.
- 13.
Cox JSG, Beach JE, Blair AMJN, Clarke AJ, King J, Lee TB, Loveday Dee, Moss GF, Orr
TSC, Ritchie JT, Sheard P. Disodium cromoglycate (Intal). Adv Drug Res 1970;5:115-196.
- 14. Cox J. Disodium cromoglycate. Mode of action and its possible relevance to the clinical use of the drug. Br J Dis Chest 1971;65:189-204.
- 15. Cuevas M, Marmier S, Girard J-P. Analysis of immunological features of intrinsic and extrinsic asthma and clinical response to disodium cromoglycate. Clin Allergy 1977;7:515-25.
- 16. Dente FL, del Bono L, del Bono N, Ruggieri F, Patalano F. Effect of nedocromil sodium and sodium cromoglycate on bronchospasm due to non-specific stimuli (physical exercise, methacholine, hyperventilation of cold air). Folia Allergol Immunol Clin 1987;34(6):329-38.
- 17.
Dickson W, Cole M. Severe asthma in children - A 10-year follow-up. In the mast cell.
Edited by Pepys J and Edwards AM. Pitman Medical 1979;343.
- 18.
Dixon CMS, Ind PW. Inhaled sodium metabisulphite induced bronchoconstriction:
inhibition by nedocromil sodium and sodium cromoglycate. Br J Clin Pharmacol 1990;30(3):371-6.
- 19. Fanta CH, McFadden ER, Ingram RH. Effects of cromolyn sodium on the response to respiratory heat loss in normal subjects. Am Rev Respir Dis 1981;161-4.
- 20. Frith PA, Ruffin RE, Juniper EF, Dolovich J, Hargreave FE. Inhibition of allergen-induced asthma by three forms of sodium cromoglycate. Clin Allergy 1981;11(1):67-77.
- 21.
Geller-Bernstein C, Levin S. Sodium cromoglycate pressurized aerosol in childhood asthma.
Curr Ther Res 1983;34(2):345-9.
- 22. Goose J, Blair AMJN. Passive cutaneous anaphylaxis in the rat, induced with two homologous reagin-like antibody sera and its specific inhibition with disodium cromoglycate. Immunology 1969;16:749-60.
- 23. Hamm T, Petro W, Bauer PC, Konietzko N. Protective effect of an antiasthmatic agent in allergen-provoked asthma. (German, English abstract) Prax Klin Pneumol 1987;41:651-2.
- 24.
Harries MC. Bronchial irritant receptors and possible new actions for cromolyn sodium. Ann
Allergy 1981;46:156-8.
- 25. Juniper EF, Latimer KM, Morris MM, Roberts RS, Hargreave FE. Airway responses to hyperventilation of cold dry air: duration of protection by cromolyn sodium. J Allergy Clin Immunol 1986;78(3pt1):387-91.
- 26. Khurana S, Hyde JS. Cromolyn sodium, 5-6 years later. Ann Allergy 1977;39:94-8.
- 27. Lapras M, Gillet A. Absence of effects of sodium cromoglycate on the reproduction and development of laboratory animals (fertility, teratogenicity, embryotoxicity, peri- and post-natal effects). J Pharm Med 1982;8:27-43.
- 28. Latimer KM, Roberts R, Morris MM, Hargreave FE. Inhibition by sodium cromoglycate of bronchoconstriction stimulated by respiratory heat loss: comparison of pressurised aerosol and powder. Thorax 1984;39(4):277-81.
- 29. Lozewicz S, Robertson CF, Costello JF, Price JF. Delivery of sodium cromoglycate by pressurized aerosol. Clin Allergy 1984;14(2):187-91.
- 30. Magnussen H, Reuss G, Jorres R, Kessler K. Protective effect of disodium cromoglycate acid (DSCG) on inhalative thermal burden in asthma. Prax Klin Pneumol 1983;37:364-71.
- 31. Merrett TG. Benefit from disodium cromoglycate and its relation to IgE profiles. In the mast cell. Edited by Pepys J, Edwards AM. Pitman Medical 1979;353.
- 32. Morrison Smith J. Prolonged use of disodium cromoglycate in children and young persons -ten years experience. In the mast cell. Edited by Pepys J, Edwards AM. Pitman Medical 1979;280.
- 33. Morton AR, Ogle SL, Fitch KD. Effects of nedocromil sodium, cromolyn sodium and a placebo in exercise-induced asthma. Ann Allergy 1992;68(2):143-8.
- 34. Neale MG, Brown K, Hodder RW, Auty RM. The pharmacokinetics of sodium cromoglycate in man after intravenous and inhalation administration. Br J Clin Pharm 1986;22:373-82.
- 35.
Petro W, Hamm T, Bauer PC, Konietzko N. Protection against allergen-induced asthma:
comparison between nedocromil-sodium, sodium cromoglycate and placebo. (German, English translation) Atem Lungen 1986;12(2):S101-5.
- 36. Petty TL, Rollins DR, Christopher K, Good JT, Oakley R. Cromolyn sodium is effective in adult chronic asthmatics. Am Rev Respir Dis 1989;138:694-701.
- 37.
Price HV. Cromolyn sodium (Intal): post market surveillance. Immunol Allergy Practice
1986;8:33-40.
- 38. Rafferty P, Fergusson RJ, Tweedale PM, Biggs BA, Grant IWB. Effects of verapamil and sodium cromoglycate on bronchoconstriction induced by isocapnic hyperventilation. Clin Allergy 1985;15(6):531-4.
- 39. Read J, Rebuck AS. Steroid-sparing effect of disodium cromoglycate ('Intal') in chronic asthma. Med J Aust 1969;1:566-9.
- 40. Rubin AE, Alroy G, Spitzer S. The treatment of asthma in adults using sodium cromoglycate pressurized aerosol: a double-blind controlled trial. Curr Med Res Opin 1983;8(8):553-8.
- 41.
Schoeffel RE, Anderson SD, Lindsay DA. Sodium cromoglycate as a pressurised aerosol
(Vicrom) in exercise-induced asthma. Aust NZ J Med 1983;13:157-61.
- 42. Settipane GA, Klein DE, Boyd GK, Sturan JH, Freye HB, Weltman JK. Adverse reactions to cromolyn. JAMA 1979;241:811-3.
- 43. Sheppard D, Nadel JA, Boushey HA. Inhibition of sulfur dioxide-induced bronchoconstriction by disodium cromoglycate in asthmatic subjects. Am Rev Respir Dis 1981;124:257-9.
- 44. Tan WC, Cripps E, Douglas N, Sudlow MF. Protective effect of drugs on bronchoconstriction induced by sulfur dioxide. Thorax 1982;37(9):671-6.
- 45. Toogood JH et al. Changes in corticosteroid usage by chronic asthma patients during a year of cromoglycate treatment. J Allergy Clin Immunol 1973;52:334-45.
- 46.
Toogood JH. Multi-centre surveillance of long-term safety of sodium cromoglycate. Acta
Allergol 1977;32(Suppl13):44-54.
- 47. Tullett WM, Tan KM, Wall RT, Patel KR. Dose-response effect of sodium cromoglycate pressurised aerosol in exercise induced asthma. Thorax 1985;40(1):41-4.
- 48.
Walker SR et al. The fate of (14C) disodium cromoglycate in man. J Pharm Pharmacol
1972;24:525-31.
- 49.
Wilson J. The use of sodium cromoglycate during pregnancy. Acta Therapeutica
1982;8(2):45-51.
- 50. Wheatley D. Sodium cromoglycate in aerosol form in regular users of bronchodilator drugs. Curr Med Res Opin 1983;8(5):333-7.
BIBLIOGRAPHY "B"
- 1. Balfour-Lynn, L., Tooley, M. & Godgrey, S. (1981) Relationship of exercise-induced asthma to clinical asthma in childhood. Arch. Dis. Child. 56:450
- 2.
Blumenthal, M.M. et al. (1973) Cromolyn in extrinsic and intrinsic asthma. J. Allergy.
Clin. Immunol. 52:105
- 3. Bresllin, F.J., McFadden, E.R. & Ingram, R.H. (1980) The effects of cromolyn sodium on the airway response to hyperpnea and cold air in asthma. Am. Rev. Respir. Dis. 122:11
- 4. Brompton Hospital/Medical Research Council collaborative trial (1972) Long term study of DSCG in treatment of severe extrinsic or intrinsic asthma in adults. Br. Med. J. 4:383
- 5. Cox, J. (1971) Disodium cromoglycate. Mode of action and its possible relevance to the clinical use of the drug. Br. J. Dis. Chest 65:189
- 6. Cuevas, M., Marmier, S. and Girard, J.-P. (1977) Analysis of immmunological features of intrinsic and extrinsic asthma and clinical response to DSCG. Clin. Allergy 7:515
- 7. Dahl, R. & Henriksen, J.M. (1979) Inhibition of exercise-induced bronchoconsriction by nebulised sodium cromoglycate in patients with bronchial asthma. Scand. J. Resp. Dis. 60:51
- 8. Eggelston, P.A. et al (1972) A double-blind trial of the effect of cromolyn sodium on exercise-induced bronchospasm. J. Allergy Clin. Immunol. 50:57
- 9. Fanta, C.H., McFadden, E.R. and Ingram, R.H. (1981) Effects of cromolyn sodium on the response to respiratory heat loss in normal subjects. Am. Rev. Respir. Dis. 123:161
- 10. Harries, M.C. (1981) Bronchial irritant receptors and a possible new actions for cromolyn sodium. Ann. Allergy 46:156
- 11. Hendrick, D.J., Davies, R.J. and Pepys, J. (1976) Baker's asthma. Clin Allergy. 6:241
- 12. Karr, R.M. et al (1978) Occupational asthma. J. Allergy. Clin. Immunol. 61:54
- 13. Laitinen, L.A. et al (1978) Disodium cromoglycate, sympathomimetic and anticholinergic medication in the treatment of farmer's lung. Tuberculosis and Respiratory Diseases Yearbook (Finnish Anti-Tuberculosis Asn.) 7:9
- 14. Loos, T. et al (1981) Experience with Intal in the treatment of childhood extrinsic and intrinsic bronchial asthma. Orvosi Hetilap 122:1129 (Hungarian)
- 15. Monkare, S. et al (1982) Does disodium cromoglycate prevent exacerbation of farmer's lung? Allergy. 37:217
- 16. Morton, A. TR. and Fitch, K.D. (1974) Sodium cromoglycate BP in the prevention of exercise-induced asthma. Med. J. Aust. 2:158
- 17. Neuman, I. and Lutsky, I. (1976) Laboratory animal dander allergy: II Clinical studies and the potential protective effect of disodium cromoglycate. Ann. Allergy. 36:23
- 18. Pepys, J., Pickerking, C.A.C. and Loudon, W.G. (1972) Asthma due to inhaled clinical agents - piperazine dihydrochloride. Clin. Allergy. 2:189
- 19. Sanguinetti, C.M. et al (1982) Exercixze-induced asthma diagnosis and prevention with a metered-dose aerosol formulation of sodium cromoglycate. Respiration 43:132
- 20. Schlick, W. (1980) Long-term treatment of bronchial asthma with disodium cromoglycate (Intal). Wiener. Med. Wschr. 130:636 (German)
- 21. Silverman, M. and Andrea, T. (1972) Time course of effect of disodium cromoglycate on exercise-induced asthma. Arch. Dis. Child. 47:419
- 22. Thiel, H. and Ulmer, W.T. (1980) Baker's asthma: development and possibility for treatment. Chest. 78:400
- 23.
Zuskin, E. and Bouhuys, A. (1976) Protective effect of disodium cromoglycate against airway construction induced by hemp dust. Extract. J. Allergy. Clin. Immunol. 57:573
BIBLIOGRAPHY "C"
- 1.
Cox, J.S.G., Beach, J.E., Blair, A.M.J.N., Clarke, A.J., King, J., Lee, T.B., Loveday,
D.E.E., Moss, G.F., Orr, T.S.C., Ritchie, JT., Sheard, P. (1970) Disodium cromoglycate (Intal) Adv. Drug Res. 5:115-196
- 2. Lapras, M., & Gillet, A. (1982) Absence of effects of sodium cromoglycate on the reproduction and development of laboratory animals (fertility, teratogenicity, embryotoxicity, peri and post-natal effects). J. Pharm. Med. 8:27-43 (French/English)
- 3.
Wilson, J. (1982) The use of sodium cromoglycate during pregnancy. J. Pharm. Med.
8:45-51 (French/English)