


Product Monograph - Jamp Doxepin Tablets
RECENT MAJOR LABEL CHANGES
| 4 DOSAGE AND ADMINISTRATION, 4.5 Missed dose | 2026-08 |
|---|
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed. RECENT MAJOR LABEL CHANGES .............................................................................................. 2
TABLE OF CONTENTS ................................................................................................................ 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
- 1
INDICATIONS ..................................................................................................... 4
- 1.1 Pediatrics ........................................................................................................... 4
- 1.2 Geriatrics ........................................................................................................... 4
- 2 CONTRAINDICATIONS ........................................................................................ 4
- 4
DOSAGE AND ADMINISTRATION ........................................................................ 4
- 4.1 Dosing Considerations ........................................................................................ 4
- 4.2 Recommended Dose and Dosage Adjustment .................................................... 4
4.5 Missed dose ....................................................................................................... 5
- 5 OVERDOSAGE .................................................................................................... 5
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING........................ 7
- 7
WARNINGS AND PRECAUTIONS ......................................................................... 7
- 7.1 Special Populations ............................................................................................ 9
- 7.1.1 Pregnant Women ........................................................................................... 9
- 7.1.2 Breast-feeding ..............................................................................................10
- 7.1.3 Pediatrics………………………………………………………………………………………………………..10
- 7.1.4 Geriatrics………………………………………………………………………………………………………..10
- 8
ADVERSE REACTIONS ....................................................................................... 10
- 8.1 Adverse reaction overview ............................................................................... 10
- 8.2 Clinical Trial Adverse Reactions......................................................................... 10
- 8.3 Less Common Clinical Trial Adverse Reactions................................................... 12
- 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ............................................................................................. 13
- 8.5 Post-Market Adverse Reactions........................................................................ 13
- 9
DRUG INTERACTIONS ....................................................................................... 14
- 9.1 Serious drug interactions .................................................................................. 14
- 9.2 Drug Interactions Overview .............................................................................. 14
- 9.3 Drug-Behavioural Interactions .......................................................................... 14
- 9.4 Drug-Drug Interactions ..................................................................................... 14
- 9.5 Drug-Food Interactions..................................................................................... 16
- 9.6 Drug-Herb Interactions ..................................................................................... 16
- 9.7 Drug-Laboratory Test Interactions .................................................................... 16
- 10
CLINICAL PHARMACOLOGY .............................................................................. 16
- 10.1 Mechanism of Action........................................................................................ 16
- 10.2 Pharmacodynamics .......................................................................................... 17
- 10.3 Pharmacokinetics ............................................................................................. 18
- 11 STORAGE, STABILITY AND DISPOSAL ................................................................ 20
- 12 SPECIAL HANDLING INSTRUCTIONS .................................................................. 20
PART II: SCIENTIFIC INFORMATION ......................................................................................... 21
- 13 PHARMACEUTICAL INFORMATION ................................................................... 21
- 14
CLINICAL TRIALS............................................................................................... 21
- 14.1 Clinical Trial by Indication ................................................................................. 21
- 14.2 Comparative Bioavailability Studies……………………………………………………………………23
- 15 MICROBIOLOGY ............................................................................................... 23
- 16 NON-CLINICAL TOXICOLOGY ............................................................................ 23
- 17 SUPPORTING PRODUCT MONOGRAPHS………………………………………………………….24
Patient Medication Information ............................................................................................. 25
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Doxepin Tablets (doxepin tablets) is indicated for:
- the treatment and symptomatic relief of insomnia characterized by frequent nocturnal awakening, and/or early morning awakenings.
The clinical trials performed in support of efficacy were up to 1 month duration in adults and 3 months in duration in the elderly (≥ 65 years of age).
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (≥ 65 years of age): During clinical trials, no overall differences in safety or effectiveness were observed in elderly and adult patients, however greater sensitivity of some older individuals cannot be ruled out.
2 CONTRAINDICATIONS
JAMP Doxepin Tablets is contraindicated in patients:
- with known intolerance or hypersensitivity to doxepin hydrochloride, other dibenzoxepine compounds or to any ingredient in the formulation or component of the container. For a complete listing, see the 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- with untreated narrow angle glaucoma.
- with severe urinary retention.
- currently taking monoamine oxidase inhibitors (MAOIs) or who have used MAOIs within the past two weeks. Serious side effects and even death have been reported following the concomitant use of certain drugs with MAOIs.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
JAMP Doxepin Tablets should be taken within 30 minutes of bedtime. To minimize the potential for next day effects, JAMP Doxepin Tablets should not be taken within 3 hours of a meal (see 10.3 Pharmacokinetics). If symptoms fail to remit after 7-10 days, alternative primary psychiatric or medical illness should be considered.
4.2 Recommended Dose and Dosage Adjustment
Adults: The recommended dose of JAMP Doxepin Tablets for adults is 6 mg once daily. A 3 mg once daily dose may be appropriate for some patients, if clinically indicated.
Geriatrics (≥ 65 years old): The recommended starting dose of JAMP Doxepin Tablets in geriatric patients is 3 mg once daily. The daily dose can be increased to 6 mg, if clinically indicated.
The safety and efficacy of doxepin in the treatment of insomnia at doses higher than 6 mg has not been established and is therefore not recommended.
Pediatrics (< 18 years of age): JAMP Doxepin Tablets is not indicated for patients less than 18 years of age.
Use in Patients with Hepatic Impairment: Patients with hepatic impairment may display higher doxepin concentrations than healthy individuals. Initiate JAMP Doxepin Tablets treatment with 3 mg in patients with hepatic impairment and monitor closely for adverse daytime effects.
4.5 Missed dose
If a dose is missed, the patient should be instructed to take the next dose when it is due. The patient should be instructed to not make up for a missed dose by taking double dose next time.
5 OVERDOSAGE
Doxepin is routinely administrated for indications other than insomnia at doses 10- to 50-fold higher than the highest recommended dose of JAMP Doxepin Tablets (6 mg).
Symptoms: Excessive drowsiness leading to minor alterations of consciousness and even unresponsiveness could be an early indication of excessive dosage. However, overdosage with doxepin hydrochloride is more likely to be manifested by increased psychomotor agitation and convulsions leading to apnea and coma. The electrocardiogram (ECG) changes (broadening of QRS and T-wave abnormalities) tend to be a late finding and are not always accompanied by cardiovascular hemodynamic changes.
The following adverse effects have been associated with use of doxepin at doses higher than 6 mg.
Anticholinergic Effects: constipation and urinary retention
Central Nervous System: disorientation, hallucinations, numbness, paresthesias, extrapyramidal symptoms, seizures, tardive dyskinesia
Cardiovascular: hypotension
Gastrointestinal: aphthous stomatitis, indigestion
Endocrine: raised libido, testicular swelling, gynecomastia in males, enlargement of breasts and galactorrhea in the female, raising or lowering of blood sugar levels, and syndrome of inappropriate antidiuretic hormone secretion
Other: weight gain, sweating, flushing, jaundice, alopecia, exacerbation of asthma, and hyperpyrexia (in association with chlorpromazine)
Treatment: In general, treatment of overdosage should be symptomatic and supportive. Cardiac arrhythmias and central nervous system (CNS) involvement pose the greatest threat with tricyclic antidepressant overdosage and may occur suddenly even when initial symptoms appear to be mild. Therefore, patients who may have ingested an overdosage of doxepin hydrochloride, particularly children, should be hospitalized and kept under close surveillance.
If the patient is conscious, induced emesis followed by gastric lavage, with appropriate precautions to prevent pulmonary aspiration, should be accomplished as soon as possible. Following lavage, activated charcoal may be administered to reduce absorption. An adequate airway should be established in comatose patients and assisted ventilation instituted, if necessary. The possibility of occurrence of seizures should be kept in mind. External stimulation should be minimized to reduce the tendency to convulsions. Convulsions, should they occur, may respond to standard anticonvulsant therapy. However, barbiturates should be avoided since they may potentiate respiratory depression, particularly in children, and aggravate hypotension and coma.
ECG monitoring in an intensive care unit is recommended in all patients, particularly in the presence of ECG abnormalities, and should be maintained for several days after the cardiac rhythm has returned to normal. A patient who has ingested a toxic overdose of a tricyclic antidepressant may remain medically and psychiatrically unstable for several days due to sustained excessive drug levels. Unexpected cardiac deaths have occurred up to 6 days after overdosage with other antidepressants. The QRS interval of the electrocardiogram appears to be a reliable correlate of the severity of overdosage. If the QRS interval exceeds
100 milliseconds any time during the first 24 hours after overdosage, cardiac function should be continuously monitored for 5 or 6 days. Because of its effect on cardiac conduction, digitalis should be used only with caution. If rapid digitalization is required for the treatment of congestive heart failure, special care should be exercised in using the drug.
Shock should be treated with supportive measures such as intravenous fluids, oxygen and corticosteroids. Pressor agents, such as noradrenaline (but not adrenaline), are rarely indicated and should be given only after careful consideration and under continuous monitoring.
The slow intravenous administration of physostigmine salicylate has been reported to reverse most of the cardiovascular and CNS anticholinergic manifestations of tricyclic overdose. The recommended dosage in adults has been 1 mg to 2 mg in very slow intravenous injection. In children, the initial dosage should not exceed 0.5 mg and should be adjusted to age and response. Since physostigmine has a short duration of action, administration may have to be repeated at 30 to 60 minute intervals.
Deaths by deliberate or accidental overdosage have occurred with this class of drugs. Since the propensity for suicide is high in depressed patients, a suicide attempt by other means may occur during the recovery phase. The possibility of simultaneous ingestion of other drugs should also be considered.
| For management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet, 3 mg and 6 mg of doxepin (supplied as doxepin hydrochloride) | Colloidal silicon dioxide, D&C Yellow No. 10 Aluminum Lake (6 mg tablets only), FD&C Blue No. 1, lactose monohydrate, magnesium stearate and microcrystalline cellulose. |
JAMP Doxepin Tablets is formulated as an oval shaped un-coated tablet available in two strengths, 3 mg and 6 mg, and showing the following distinguishable characteristics:
- 3 mg tablet is blue and debossed with “3” on one side and “JP” on the other side.
- 6 mg tablet is green and debossed with “6” on one side and “JP” on the other side.
JAMP Doxepin Tablets (3 and 6 mg) is supplied in white opaque HDPE bottles with white caps of 30 tablets.
7 WARNINGS AND PRECAUTIONS
General
CNS depressant effects: When taken with JAMP Doxepin Tablets, the sedative effects of other CNS depressants, sedating antihistamines and alcoholic beverages may be potentiated (see 9.4 Drug-Drug Interactions). Patients should not consume alcohol with JAMP Doxepin Tablets (see 9.4 Drug-Drug Interactions). Patients should be cautioned about potential additive effects of JAMP Doxepin Tablets used in combination with CNS depressants or sedating antihistamines.
Complex sleep-related behaviours: Complex behaviours such as “sleep-driving” (i.e., driving while not fully awake after ingestion of a hypnotic, with amnesia for the event) have been reported with hypnotics. Other potentially dangerous behaviours have been reported in patients who got out of bed after taking a sedative-hypnotic and were not fully awake, including preparing and eating food, making phone calls, leaving the house, etc. As with “sleep-driving”, patients usually do not remember these events. These events can occur in hypnotic-naive as well as in hypnotic-experienced persons. Although behaviours such as “sleep-driving” may occur with hypnotics alone at therapeutic doses, the use of alcohol and other CNS depressants with hypnotics appears to increase the risk of such behaviours, as does the use of hypnotics at doses exceeding the maximum recommended dose. Due to the risk to the patient and the community, discontinuation of JAMP Doxepin Tablets should be strongly considered for patients who report a “sleep-driving” episode or other complex behaviours episode.
Dependence/Tolerance
Potential withdrawal effects were assessed in a 35-day double blind study of adults with chronic insomnia who were randomized to placebo, doxepin 3 mg, or doxepin 6 mg. There was no indication of a withdrawal syndrome after discontinuation of doxepin treatment (3 mg or
6 mg), as measured by the Tyrer’s Symptom Checklist. Discontinuation-period emergent nausea and vomiting occurred in 5 % of subjects treated with 6 mg doxepin, versus 0 % in 3 mg and placebo subjects.
Doxepin has not been demonstrated to produce tolerance or physical dependence. In a brief assessment of adverse events observed during discontinuation of doxepin following chronic administration, no symptoms indicative of a withdrawal syndrome were observed.
Abuse potential: Doxepin is not associated with abuse potential in animals or in humans. Healthcare professionals should carefully evaluate patients for history of drug abuse and follow such patients closely, observing them for signs of misuse or abuse of doxepin (e.g., escalation of dose, drug-seeking behaviours).
Driving and Operating Machinery
Patients should be cautioned against engaging in hazardous occupations requiring complete mental alertness or motor coordination such as operating machinery or driving a motor vehicle after ingesting the drug. This includes potential impairment of the performance of such activities that may occur the day following ingestion of JAMP Doxepin Tablets.
Hepatic/Biliary/Pancreatic
The effects of hepatic impairment on the pharmacokinetics of doxepin have not been studied. Because doxepin is extensively metabolized by hepatic enzymes, patients with hepatic impairment may display higher doxepin concentrations than healthy individuals (see
- 4.2 Recommended Dose and Dosage Adjustment).
Psychiatric
Depression: JAMP Doxepin Tablets should be administered with caution when prescribed to patients with signs and symptoms of depression that could be intensified by hypnotic drugs. The potential for self-harm (e.g., intentional overdose) is high in patients with depression and thus, the least amount of drug should be available to them at any given time.
Worsening of depression and suicidal ideation: In primarily depressed patients treated with hypnotics, worsening of depression and suicidal thoughts and actions have been reported. As with other hypnotics, JAMP Doxepin Tablets should be administered with caution in patients with depression. The risk of suicide due to pre-existing psychiatric disorders remains, even when the patient's insomnia improves.
Doxepin, the active ingredient in JAMP Doxepin Tablets, is an antidepressant at doses 10- to 100-fold higher than JAMP Doxepin Tablets. Antidepressants increased the risk compared to placebo of suicidal thinking and behaviours (suicidality) in children, adolescents, and young adults in short-term studies of major depressive disorder (MDD) and other psychiatric disorders. Risk from the lower dose of doxepin in JAMP Doxepin Tablets cannot be excluded.
It can rarely be determined with certainty whether a particular instance of the abnormal behaviours listed above is drug induced, spontaneous in origin, or a result of an underlying psychiatric or physical disorder. Nonetheless, the emergence of any new behaviours sign or symptom of concern requires careful and immediate evaluation.
Renal
The effects of renal impairment on the pharmacokinetics of doxepin have not been studied. Because only small amounts of doxepin and nordoxepin are eliminated in the urine, renal impairment is not expected to result in significantly altered doxepin concentrations.
Respiratory
Patients with sleep apnea: Doxepin has not been studied in patients with obstructive sleep apnea. Since hypnotics have the capacity to depress respiratory drive, precautions should be taken if JAMP Doxepin Tablets is prescribed to patients with compromised respiratory function. In patients with severe sleep apnea, JAMP Doxepin Tablets is not recommended for use.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies of doxepin in pregnant women. JAMP Doxepin Tablets should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Administration of doxepin to pregnant animals resulted in adverse effects on offspring development at doses greater than the maximum recommended human dose (MRHD) of 6 mg/day.
When doxepin (30, 100 and 150 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, developmental toxicity (increased incidences of fetal structural abnormalities and decreased fetal body weights) was noted at ≥ 100 mg/kg/day. The plasma exposures (AUC) at the no-effect dose for embryo-fetal developmental toxicity in rats
(30 mg/kg/day) are approximately 6 and 3 times the plasma AUCs for doxepin and nordoxepin (the primary metabolite in humans), respectively, at the MRHD. When administered orally to pregnant rabbits (10, 30 and 60 mg/kg/day) during the period of organogenesis, fetal body weights were reduced at the highest dose in the absence of maternal toxicity. The plasma exposures (AUC) at the no-effect dose for developmental effects (30 mg/kg/day) are approximately 6 and 18 times the plasma AUCs for doxepin and nordoxepin, respectively, at the MRHD. Oral administration of doxepin (10, 30 and 100 mg/kg/day) to rats throughout the pregnancy and lactation periods resulted in decreased pup survival and transient growth delay at the highest dose. The plasma exposures (AUC) at the no-effect dose for adverse effects on pre- and postnatal development in rats (30 mg/kg/day) are approximately 3 and 2 times the plasma AUCs for doxepin and nordoxepin, respectively, at the MRHD.
Labor and/or Delivery: The effects of doxepin on labor and delivery in pregnant women have not been studied.
7.1.2 Breast-feeding
Doxepin is excreted in human milk after oral administration. There has been a report of apnea and drowsiness occurring in a nursing infant whose mother was taking higher dose of doxepin to treat depression. Therefore, the administration of JAMP Doxepin Tablets to nursing mothers is not recommended.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): The safety and effectiveness of doxepin in pediatric patients have not been evaluated. Therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): A total of 362 subjects who were ≥ 65 years and 86 subjects who were ≥ 75 years received doxepin in controlled clinical studies. No overall differences in safety or effectiveness were observed between these subjects and younger adult subjects but greater sensitivity of some older individuals cannot be ruled out as sleep-promoting drugs may cause confusion and over-sedation in elderly (see 4.2 Recommended Dose and Dosage Adjustment).
8 ADVERSE REACTIONS
8.1 Adverse reaction overview
The most common reported adverse drug reactions with doxepin were somnolence, sedation and nausea. There was no apparent overall relationship to dose for any adverse reaction other than for the combined adverse events of somnolence and sedation.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful for identifying and approximating rates of adverse drug reactions in real-world use.
During the doxepin clinical development program, a total of 1,017 subjects were exposed to doses of 1 mg to 6 mg of doxepin. The safety of doxepin has been evaluated in three Phase 3 long-term placebo-controlled clinical trials (ranging from 28 to 85 days) conducted in adults (n = 221) and elderly (n = 494) subjects with chronic insomnia.
The percentage of subjects discontinuing Phase 1, 2, and 3 trials for an adverse reaction was
0.6 % in the placebo group compared to 0.4 %, 1.3 %, and 0.8 % in the doxepin 1 mg, 3 mg, and 6 mg groups, respectively. No reaction that resulted in discontinuation occurred at a rate greater than 0.5 %.
Table 2 lists the treatment-emergent adverse events, regardless of causality, reported by at least 1% of subjects who received doxepin (3 mg or 6 mg) in the three long-term chronic insomnia studies (n = 221 for adult; and n = 417 for elderly).
Table 2 – Treatment-Emergent Adverse Events Reported at a Frequency ≥ 1 % of Subjects in Long-Term Chronic Insomnia Studies
System Organ Class Preferred term n (%) | Doxepin 3 mg (n = 157) | Doxepin 6 mg (n = 203) | Placebo (n = 278) | ||||||
|---|---|---|---|---|---|---|---|---|---|
System Organ Class Preferred term n (%) | Doxepin 3 mg (n = 157) | Doxepin 6 mg (n = 203) | Placebo (n = 278) | ||||||
| Blood and lymphatic system disorders | |||||||||
| Anemia | 0 | 2 (1.0) | 0 | ||||||
| Gastrointestinal disorders | |||||||||
| Nausea | 3 (1.9) | 5 (2.5) | 3 (1.1) | ||||||
| Dry mouth | 2 (1.3) | 3 (1.5) | 3 (1.1) | ||||||
| Vomiting | 0 | 3 (1.5) | 2 (0.7) | ||||||
| Stomach discomfort | 2 (1.3) | 0 | 0 | ||||||
| General disorders and administration site conditions | |||||||||
| Chest pain | 2 (1.3) | 1 (0.5) | 0 | ||||||
| Infections and infestations | |||||||||
| Upper respiratory tract infection | 3 (1.9) | 3 (1.5) | 3 (1.1) | ||||||
| Nasopharyngitis | 3 (1.9) | 1 (0.5) | 2 (0.7) | ||||||
| Gastroenteritis | 3 (1.9) | 0 | 0 | ||||||
| Tooth infection | 2 (1.3) | 0 | 1 (0.4) | ||||||
| Injury, poisoning and procedural complications | |||||||||
| Post procedural complication | 2 (1.3) | 1 (0.5) | 0 | ||||||
| Fall | 2 (1.3) | 0 | 2 (0.7) | ||||||
| Joint sprain | 2(1.3) | 0 | 1 (0.4) | ||||||
| Investigations | |||||||||
| Blood glucose increased | 2 (1.3) | 0 | 0 | ||||||
| Metabolism and nutrition disorders | |||||||||
| Anorexia | 2 (1.3) | 0 | 0 | ||||||
| Musculoskeletal and connective tissue disorders | |||||||||
| Arthralgia | 1 (0.6) | 2 (1.0) | 1 (0.4) | ||||||
| Back pain | 2 (1.3) | 1 (0.5) | 1 (0.4) | ||||||
| Nervous system disorders | |||||||||
| Somnolence | 9 (5.7) | 11 (5.4) | 12 (4.3) | ||||||
| Sedation | 1 (0.6) | 7 (3.4) | 0 | ||||||
| Somnolence and Sedation Combined | 10 (6.4) | 18 (8.9) | 12 (4.3) | ||||||
| Dizziness | 2 (1.3) | 3 (1.5) | 3 (1.1) | ||||||
| Paresthesia | 0 | 2 (1.0) | 2 (0.7) | ||||||
| Dysgeusia | 0 | 2 (1.0) | 0 | ||||||
| Psychiatric disorders | |||||||||
| Abnormal dreams | 2 (1.3) | 0 | 0 | ||||||
| Anxiety | 0 | 2 (1.0) | 0 | ||||||
| Vascular disorders | |||||||||
| Hypertension | 4 (2.5) | 1 (0.5) | 0 | ||||||
Table 3 lists the treatment-emergent adverse events, regardless of causality, by age group reported by at least 2 % of subjects who received doxepin in the three long-term chronic insomnia studies.
Table 3 – Treatment-Emergent Adverse Events Reported at a Frequency ≥ 2 % of Adults or Elderly Subjects in the Three Long-Term Chronic Insomnia Studies
Preferred Term n (%) | Adult Subjects | Elderly Subjects | ||||||
|---|---|---|---|---|---|---|---|---|
All Doxepin* (n = 148) | Placebo (n = 73) | All Doxepin* (n = 212) | Placebo (n = 205) | |||||
| Somnolence | 11 (7.4 %) | 4 (5.5 %) | 9 (4.2 %) | 8 (3.9 %) | ||||
| Nausea | 7 (4.7 %) | 0 | 1 (0.5 %) | 3 (1.5 %) | ||||
| Sedation | 2 (1.4 %) | 0 | 6 (2.8 %) | 0 | ||||
| Dizziness | 0 | 1 (1.4 %) | 5 (2.4 %) | 2 (1.0 %) | ||||
| Dry Mouth | 0 | 0 | 5 (2.4 %) | 3 (1.5 %) | ||||
| Upper Respiratory Tract Infection | 3 (2.0 %) | 1 (1.4 %) | 3 (1.4 %) | 2 (1.0 %) | ||||
| Post Procedural Complication | 3 (2.0 %) | 0 | 0 | 0 | ||||
*includes doxepin doses ranging from 3 mg to 6 mg.
Treatment-emergent adverse events generally occurred with similar incidence in adults and elderly subjects with the exception with nausea (4.7 % in adults versus 0.5 % in elderly).
8.3 Less Common Clinical Trial Adverse Reactions
The following adverse events were reported in the administration of doxepin at a frequency
< 1 % in the three long-term chronic insomnia safety and efficacy studies.
Cardiac disorders: atrioventricular block, tachycardia
Ear and labyrinth disorders: hypoacusis, motion sickness, tinnitus
Eye disorders: blepharospasm, diplopia, eye pain, vision blurred, visual disturbance
Gastrointestinal disorders: abdominal pain upper, diarrhoea, gastroesophageal reflux disease, gingival recession, toothache, tooth fracture
General disorders: fatigue, feeling abnormal, hangover, oedema peripheral, pitting oedema, sluggishness
Infections and infestations: bronchitis, eye infection, fungal infection, gastroenteritis viral, herpes zoster, infective tenosynovitis, influenza, laryngitis, lower respiratory tract infection, onychomycosis, sinusitis, tooth abscess, urinary tract infection, viral infection
Injury, poisoning and procedural complications: back injury, excoriation, foot fracture, hand fracture, skin laceration, upper limb fracture
Investigations: blood pressure decreased, electrocardiogram abnormal
Metabolism and nutrition disorders: decreased appetite, hypokalemia, increased appetite
Musculoskeletal and connective tissue disorders: joint range of motion decreased, muscle cramp, myalgia, neck pain, pain in extremity
Neoplasm benign, malignant and unspecified (including cysts and polyps): lung adenocarcinoma stage I, malignant melanoma
Nervous system disorders: ageusia, ataxia, disturbance in attention, lethargy, migraine, sleep paralysis, tremor
Psychiatric disorders: depression, elevated mood, libido decreased, nightmare
Renal and urinary disorders: enuresis
Reproductive system and breast disorders: breast cyst
Respiratory, thoracic and mediastinal disorders: cough, nasal congestion, nasopharyngeal disorder, pharyngolaryngeal pain, sinus congestion
Skin and subcutaneous tissue disorders: dermatitis contact, erythema, pruritus generalized, rash, rosacea, skin lesion
Vascular disorders: blood pressure inadequately controlled, hematoma
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
There were no clinically relevant findings in the mean values and mean changes in clinical laboratory data after any of the treatments.
8.5 Post-Market Adverse Reactions
The following adverse events have been reported in users of doxepin in the post marketing period. These adverse events are compiled from spontaneous reports and are listed regardless of frequency and whether or not a causal relationship with doxepin has been established.
Adverse events previously observed in clinical trials are not duplicated below.
Cardiac disorders: palpitations
Eye disorders: dry eye, lacrimation decreased, ocular hyperemia, visual acuity reduced
Gastrointestinal disorders: abdominal discomfort, bowel movement irregularity, dyspepsia, flatulence
General disorders: energy increased, epistaxis, feeling drunk, hypotrichosis, irritability, stress symptoms
Injury, poisoning and procedural complications: intentional overdose
Investigations: dysuria, hyperglycemia, hypoglycemia, swollen tongue, urine output decreased, urine output increased, weight increased
Musculoskeletal and connective tissue disorders: muscle spasms
Nervous system disorders: drowsiness, dyskinesia, head discomfort, nervousness, poor quality sleep, psychomotor hyperactive, restless leg syndrome, restlessness
Psychiatric disorders: amnesia, hallucination, insomnia, mental impairment, mood altered, sleep disorder, suicidal ideation, suicidal thoughts, thinking abnormal
Renal and urinary disorders: micturition urgency, urinary hesitation
Respiratory, thoracic and mediastinal disorders: dyspnea, hoarseness, pharyngeal hypoesthesia, pharyngeal edema, throat irritation
Skin and subcutaneous tissue disorders: hyperhidrosis, night sweats, rash generalized
Vascular disorders: hot flush
9 DRUG INTERACTIONS
9.1 Serious drug interactions
|
|---|
9.2 Drug Interactions Overview
Doxepin is primarily metabolized by hepatic cytochrome P450 isozymes CYP2C19 and CYP2D6, and to a lesser extent, by CYP1A2 and CYP2C9. Inhibitors of these isozymes may increase the exposure of doxepin. Doxepin is not an inhibitor of any CYP isozymes at therapeutically relevant concentrations. The ability of doxepin to induce CYP isozymes is not known.
Since doxepin is metabolized by CYP2C19 and CYP2D6, inhibitors of these CYP isozymes may increase the exposure of doxepin.
9.3 Drug-Behavioural Interactions
JAMP Doxepin Tablets may potentiate the sedative effects of alcohol. Patients should not consume alcohol with JAMP Doxepin Tablets.
9.4 Drug-Drug Interactions
JAMP Doxepin Tablets may potentiate the sedative effects of sedating antihistamines and other CNS depressants.
Table 4 – Established or Potential Drug-Drug Interactions
| Proper/common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Proper/common name | Source of Evidence | Effect | Clinical comment |
| CNS Depressants (e.g., barbiturates), and Sedating Antihistamines | T | Potential additive effects of JAMP Doxepin Tablets used in combination with CNS depressants or sedating antihistamines. | Patients should be cautioned about this effect. |
| Cimetidine | CT | When cimetidine 300 mg BID was co-administrated with a single dose of doxepin 6 mg, there was approximately a 2-fold increase in doxepin Cmax and AUC compared to doxepin given alone. | A maximum dose of 3 mg is recommended in adults and elderly when cimetidine is co-administered with JAMP Doxepin Tablets. |
| Sertraline | CT | Following co-administration of doxepin 6 mg with sertraline 50 mg (at steady-state), a modest pharmacokinetic drug interaction was observed; the doxepin mean AUC0-∞ and Cmax estimates were approximately 21% and 32% higher, respectively, than those obtained following administration of doxepin alone. | – |
Inhibitors or substrates of CYP2D6 (e.g., quinidine, selective serotonin reuptake inhibitors [SSRIs]) | T | May increase the plasma concentration of TCAs when administered concomitantly. | – |
| Phenytoin | T | Potential phenytoin toxicity when administered concomitantly, as phenytoin and doxepin use the same CYP2C19 metabolism pathway | |
| Sympathomimetic agents (e.g., ephedrine, phenylephrine and phenylpropanolamine) | T | Potential exaggerated symptoms of hypertension and tachycardia. | The literature reports these potential symptoms as likely dose related and may not be appear with doses lower than 25 mg/day. Hence, close supervision and careful adjustment of dosages is required when doxepin is administered with sympathomimetic agents. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Doxepin is readily absorbed from the gastrointestinal tract. When administered with a high-fat meal, the AUC for a single 6 mg dose was increased by 41 % and the Cmax was 15 % higher than when given in a fasted state. Additionally, compared to the fasted state, the time to reach maximum plasma concentration (Tmax) was delayed by approximately 3 hours. Therefore, for faster onset and to minimize the potential for next day effects, it is recommended not to take JAMP Doxepin Tablets within 3 hours of a meal (see 4.1 Dosing Considerations and 10.3 Pharmacokinetics).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
The exact mechanism by which doxepin exerts its sleep maintenance effect is unknown but it is well established that doxepin is one of the most potent H1 antagonist and has a substantial selectivity for H1 receptors (Ki < 1 nM) versus other CNS and peripheral targets. Doxepin has an affinity toward the human 5-HT2a receptor; this property could play a role in promoting sleep maintenance, as several studies have proposed that antagonism at this site promotes restorative Stage III-IV sleep.
10.2 Pharmacodynamics Cardiovascular
Cardiac safety: In a thorough QTc prolongation study in healthy subjects, doxepin had no effect on QT intervals or other electrocardiographic parameters after multiple daily doses of 6 mg or 50 mg.
In vitro studies: The effect of doxepin on IKr channels (encoded by hERG; human Ether-à-go-go Related Gene) has been investigated. Doxepin was found to inhibit IHERG channels with an IC50 of 6.5 ± 1.4 mcM and native IKr with an IC50 of 4.4 ± 0.6 mcM. This concentration is approximately 1300-fold higher than the concentration reached with the highest strength of doxepin (6 mg tablets, approximately 3.4 nM Cmax=1.094 ng/mL).
In vivo studies: Doxepin elicits either positive or negative inotropic effects depending on species, decreases in blood pressure, and dysrhythmias characterized by broadening of the QRS complex and QT prolongation. In studies where plasma concentrations are reported, these events typically occur at concentrations well in excess of 1000 ng/mL, or more than 1000 times the maximum mean concentrations (at 6 mg).
Clinical electrocardiography studies: In a double-blind, randomized, placebo-controlled, parallel group study in healthy subjects (n = 44-50/treatment arm), serial ECG recordings were collected on day 7 of treatment with doxepin at a therapeutic dose of 6 mg and a supratherapeutic dose of 50 mg. Doxepin 6 mg and doxepin 50 mg did not affect the QTc interval, the QRS duration, or the PR interval. Heart rate was not affected at the 6 mg dose, but statistically significant increases in heart rate were observed at the 50 mg dose, with a maximum placebo-adjusted mean change from baseline of 6.5 bpm (90% CI 4.3, 8.6).
Doxepin was associated with a blood pressure-lowering effect. Serial blood pressure measurements were performed on day 1 of treatment at predose and at 2, 4, 8, 12, and 24 h post-dosing. Doxepin 6 mg was associated with a statistically significant placebo-adjusted decrease from baseline in systolic blood pressure at 4 h post-dosing: mean -2.92 mmHg (90 % CI
-5.39, -0.45). Statistically significant reductions in diastolic blood pressure were reported at 4, 8, and 12 h post-dosing with doxepin 6 mg, with a maximum decrease at 8 h post-dosing: mean -
4.67 mmHg (90 % CI -6.78, -2.55).
Doxepin 50 mg was associated with statistically significant placebo-adjusted decreases from baseline in systolic blood pressure at all post-dose time points on day 1. The largest observed decrease in systolic blood pressure occurred at 8 h post-dose: mean -7.09 mmHg (90 % CI -9.56,
-4.62). Diastolic blood pressure was significantly reduced at 2, 4, 8, and 12 h post-dosing in the doxepin 50 mg group. The maximum observed decrease in diastolic blood pressure occurred at 8 h post-dosing: mean -6.68 mmHg (90 % CI -8.80, -4.57).
The Cmax and AUC values of doxepin following treatment with the 50 mg dose for 7 days were 12-fold higher than for the 6 mg dose.
Studies Pertinent to Safety Concerns for Sleep-promoting Drugs
Residual Pharmacological Effect in Insomnia Trials: Five randomized placebo-controlled studies in adults and the elderly assessed next-day psychomotor function within 1 hour of awakening utilizing the digit-symbol substitution test (DSST), symbol copying test (SCT), and visual analog scale (VAS) for sleepiness, following night time administration of doxepin.
In a one-night, double-blind study conducted in 565 healthy adult subjects experiencing transient insomnia, doxepin 6 mg showed modest negative changes in SCT and VAS.
In a 35-day, double-blind, placebo-controlled, parallel group study of doxepin 3 and 6 mg in 221 adults with chronic insomnia, small decreases in the DSST and SCT occurred in the 6 mg group.
In a 3-month, double-blind, placebo-controlled, parallel group study in 240 elderly subjects with chronic insomnia, doxepin 1 mg and 3 mg was comparable to placebo on DSST, SCT, and VAS.
10.3 Pharmacokinetics
The pharmacokinetics of doxepin 3 mg and 6 mg have been characterized in healthy subjects.
Table 5 – Summary of Doxepin Pharmacokinetic Parameters in Healthy Volunteers Following a Single Dose of 6 mg
Cmax (ng/mL) | Tmax (h) | t½ (h) | AUC0-∞ (ng*h/mL) | |
|---|---|---|---|---|
Single dose mean n = 16 | 0.8864 (59.4) | 3.5 (2.0 – 6.0) | 15.32 (31.3) | 15.19 (69.1) |
Estimates presented are arithmetic mean (CV %) for AUC, Cmax, and t1/2 and median (range) for Tmax.
Absorption: After oral administration of a 6 mg dose to fasted healthy subjects, doxepin plasma concentrations increase rapidly, with peak concentrations (median Tmax) occurring 3.5 hours postdose. Peak plasma concentrations (Cmax) and total exposure (AUC) of doxepin increased in a dose-proportional manner for 3 mg and 6 mg doses.
Doxepin is readily absorbed from the gastrointestinal tract. When administered with a high-fat meal, the AUC for a single 6 mg dose was increased by 41 % and the Cmax was 15 % higher than when given in a fasted state. Additionally, compared to the fasted state, the time to reach maximum plasma concentration (Tmax) was delayed by approximately 3 hours. Therefore, for faster onset and to minimize the potential for next day effects, it is recommended not to take JAMP Doxepin Tablets within 3 hours of a meal.
Distribution: Doxepin is highly lipophilic and widely distributed throughout the body tissues. The mean apparent volume of distribution following a single 6 mg oral dose of doxepin in healthy subjects was 11,930 liters. Doxepin is approximately 80% bound to plasma proteins.
Metabolism: Following oral administration, doxepin is extensively metabolized by oxidation and demethylation. The primary metabolite is N-desmethyldoxepin (nordoxepin). The primary metabolites undergo further biotransformation to glucuronide conjugates. In vitro studies have shown that CYP2C19 and CYP2D6 are the major enzymes involved in doxepin metabolism, and that CYP1A2 and CYP2C9 are involved to a lesser extent.
In animals, data shows that doxepin is well absorbed, widely distributed, moderately protein bounded, and undergoes extensive Phase I and Phase II metabolism, the most important pathways being demethylation, hydroxylation and glucuronidation. Doxepin metabolism appears to be similar for humans and animal species and is isomer specific, with demethylation reactions occurring for both isomers primarily via CYP2C19 (with contribution of 1A2, 2C9 and possibly 3A4), while only the E isomer is hydroxylated via CYP2D6. Doxepin, as well as oxidative metabolites and conjugates of doxepin and its isomers are rapidly eliminated and the majority of drug products are recovered in urine.
Excretion: Doxepin is excreted in the urine mainly in the form of glucuronide conjugates. Less than 3% of a doxepin dose is excreted in the urine as parent compound or nordoxepin. The apparent terminal half-life (t1/2) of doxepin is 15.3 hours and 31 hours for nordoxepin.
Special Populations and Conditions
- Pediatrics: The pharmacokinetics of doxepin have not been studied in subjects under 18 years of age.
- Geriatrics: The pharmacokinetics of doxepin have not been studied in elderly subjects. Elimination of doxepin may be slower and the terminal half-life may be longer in the elderly, which may result in drug accumulation and a greater risk of undesirable effects.
- Gender: No gender effect was observed in healthy subject/patients after repeated administration of doxepin.
- Hepatic Insufficiency: No studies have been conducted to evaluate the effect of hepatic disease on the pharmacokinetics of doxepin. Because doxepin is extensively metabolized by hepatic enzymes, patients with hepatic insufficiency may display higher doxepin concentrations than healthy individuals.
- Renal Insufficiency: No studies have been conducted to evaluate the effect of renal disease on the pharmacokinetics of doxepin. Because only small amounts of doxepin and nordoxepin are eliminated in the urine, renal impairment would not be expected to result in significantly altered doxepin concentrations.
- Genetic Polymorphism: Poor metabolizers of CYP2C19 and CYP2D6 may have higher doxepin plasma levels than normal subjects.
- Drug Interactions: Since doxepin is metabolized by CYP2C19 and CYP2D6, inhibitors of theses CYP isozymes may increase the exposure of doxepin.
11 STORAGE, STABILITY AND DISPOSAL
Keep JAMP Doxepin Tablets out of reach and sight of children.
Store JAMP Doxepin Tablets at room temperature between 15°C and 30°C. Protect from light.
12 SPECIAL HANDLING INSTRUCTIONS
Not applicable
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: doxepin hydrochloride
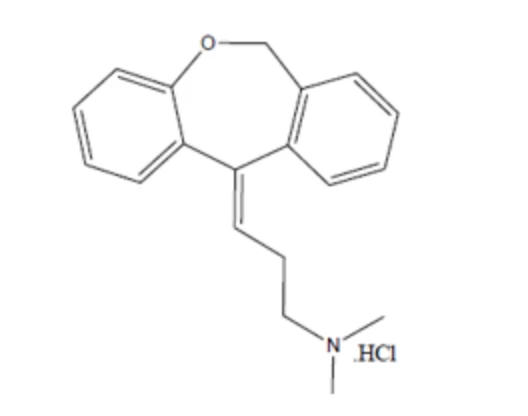
Chemical name: 1) 3-Dibenz[b,e]oxepin-11(6H)-ylidene-N,Ndimethyl-1-propanamine HCl
- 2) N,N-dimethyldibenz[b,e]oxepindelta11(6H),gamma- propylamine HCl
- 3) 11-(3-dimethylaminopropylidene)-6,11-dihydrodibenz[b,e]oxepin HCl
The drug substance is an isomeric mixture.
Molecular formula and molecular mass: C19H21NO·HCl and 315.84 g/mol Structural formula:
Physicochemical properties: Doxepin hydrochloride is a white or almost white crystalline powder, that is freely soluble in water, alcohol and methylene chloride.
14 CLINICAL TRIALS
14.1 Clinical Trial by Indication
Insomnia
The efficacy of doxepin for improving sleep maintenance was supported by six randomized, double-blind studies up to 3 months in duration that included 1,423 subjects, 18 to 93 years of age, with chronic (n = 858) or experimentally induced transient (n = 565) insomnia. Doxepin was evaluated at doses of 1 mg, 3 mg, and 6 mg relative to placebo in inpatient (sleep laboratory) and outpatient settings.
The primary efficacy measures for assessment of sleep maintenance were the objective and subjective time spent awake after sleep onset (respectively, objective Wake After Sleep Onset [WASO] and subjective WASO).
Subjects in studies of chronic insomnia were required to have at least a 3-month history of insomnia.
Rebound Insomnia Effects
Rebound insomnia, defined as a worsening in WASO compared with baseline following discontinuation of treatment, was assessed in a double-blind, 35-day study (followed by 2 days of drug discontinuation – i.e.: Day 36 and 37) in adults with chronic insomnia. Doxepin 3 mg and 6 mg showed little evidence of rebound insomnia in the two nights following discontinuation.
However, there was evidence of mild discontinuation effects on latency to persistent sleep (LPS)
in the two nights following doxepin discontinuation.
Study Results
Chronic Insomnia
Adults: A randomized, double-blind, parallel-group study was conducted in adults (n = 221) with chronic insomnia. Doxepin 3 mg and 6 mg was compared to placebo out to 30 days. Doxepin
- 3 mg and 6 mg were superior to placebo on objective WASO and TST (total sleep time). Doxepin 3 mg was superior to placebo on subjective WASO at night 1 only. Doxepin 6 mg was superior to placebo on subjective WASO at night 1, and nominally superior at some later time points out to Day 30. Doxepin 3 mg was superior to placebo on subjective TST at night 1 only. Doxepin 6 mg was superior to placebo on subjective TST at night 1, and at some later time points. On other secondary subjective outcome measures a similar pattern was observed, suggesting superior efficacy of the doxepin 6 mg dose compared to the 3 mg dose.
Elderly: Elderly subjects with chronic insomnia were assessed in two parallel-group studies.
The first randomized, double-blind study assessed doxepin 1 mg and 3 mg relative to placebo for 3 months in inpatient and outpatient settings in elderly subjects (n = 240) with chronic insomnia. Doxepin 3 mg, but not 1 mg, was superior to placebo on objective and subjective WASO. The second randomized, double-blind study assessed doxepin 6 mg relative to placebo for 4 weeks in an outpatient setting in elderly subjects (n = 254) with chronic insomnia. On subjective WASO, doxepin 6 mg was superior to placebo.
Transient Insomnia
Healthy adult subjects (n = 565) experiencing transient insomnia (induced by a 3 hour phase advance) during the first night in a sleep laboratory were evaluated in a randomized, double-blind, parallel-group, single-dose study of doxepin 6 mg relative to placebo. Doxepin 6 mg was superior to placebo on objective WASO and subjective WASO.
- 14.2 Comparative Bioavailability Studies
A double-blinded, randomized, two-treatment, two-period, two-sequence, crossover, single dose, oral comparative bioavailability study of JAMP Doxepin Tablets 6 mg tablets (JAMP Pharma Corporation) and SILENOR® 6 mg tablets (Paladin Labs Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 38 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Doxepin (1 x 6 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (pg·h/mL) | 16626.98 19382.38 (56.99) | 15051.15 17907.41 (62.65) | 110.5 | 101.9 - 119.7 |
AUCI (pg·h/mL) | 18100.69 21196.00 (58.07) | 16523.94 19575.17 (61.36) | 109.5 | 101.7 - 118.0 |
Cmax (pg/mL) | 1095.70 1285.93 (63.40) | 945.49 1129.63 (71.57) | 115.9 | 102.3 - 131.2 |
Tmax3 (h) | 3.67 (1.50 – 6.00) | 3.50 (1.50 – 5.50) | ||
T1/24 (h) | 18.50 (34.03) | 18.38 (28.63) | ||
1 JAMP Doxepin Tablets (doxepin as doxepin hydrochloride) tablets, 6 mg (JAMP Pharma Corporation)
2 SILENOR® (doxepin as doxepin hydrochloride) tablets, 6 mg (Paladin Labs Inc. Canada)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Repeat Dose Toxicity: In multiple-dose studies in rats, clinical signs of CNS depression were observed, with the addition of decreases in body weight and food consumption. However, there was no consistent evidence of target organ toxicity. Doxepin-related decreased body weight and body weight gain was also noted in animals receiving 100 mg/kg/day. Alkaline phosphatase was increased in males at 100 mg/kg/day. There were no doxepin-related macroscopic findings in either sex. There were no effects on hematology, coagulation, or urinalysis parameters. Possible doxepin-related organ weight changes were present in the liver, spleen, and thymus. Increases in liver weight were present in males and females at 25, 50, and 100 mg/kg/day. Decreased spleen weights were observed in males and females at 100 mg/kg/day and in females only at 25 and 50 mg/kg/day. No correlative microscopic findings were present in the livers or spleens. Thymus weight was decreased in both sexes at 100 mg/kg/day. These decreases in thymus weights corresponded with minimal to mild lymphoid depletion microscopically.
Carcinogenicity: No evidence of carcinogenic potential was observed when doxepin was administered orally to hemizygous Tg.rasH2 mice for 26 weeks at doses of 25, 50, 75 and 100 mg/kg/day. Doxepin has shown no oncogenic effect when administered daily to rats for 104 weeks at doses of 10, 30 and 75 mg.
Genotoxicity: Doxepin was negative in in vitro (bacterial reverse mutation, chromosomal aberration in human lymphocytes) and in vivo (rat micronucleus) assays.
Reproductive and Developmental Toxicology: When doxepin (10, 30 and 100 mg/kg/day) was orally administered to male and female rats prior to, during and after mating, adverse effects on fertility (increased copulatory interval and decreased corpora lutea, implantation, viable embryos and litter size) and sperm parameters (increased percentages of abnormal sperm and decreased sperm motility) were observed. The plasma exposures (AUC) for doxepin and nordoxepin at the no-effect dose for adverse effects on reproductive performance and fertility in rats (10 mg/kg/day) are less than those in humans at the maximum recommended human dose of 6 mg/day (approx. 53 to 61-fold).
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. SILENOR®, (tablets, 3 mg and 6 mg), Control 302847, product monograph, Knight Therapeutics Inc. (2026-01-22)