


Product Monograph - Jamp Ondansetron ODT
RECENT MAJOR LABEL CHANGES
N/A
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................... 2
TABLE OF CONTENTS ................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
- 1
INDICATIONS ................................................................................................................. 4
- 1.1 Pediatrics .................................................................................................................. 4
- 1.2 Geriatrics .................................................................................................................. 4
- 2 CONTRAINDICATIONS .................................................................................................... 5
- 4
DOSAGE AND ADMINISTRATION .................................................................................... 5
- 4.1 Dosing Considerations .............................................................................................. 5
- 4.2 Recommended Dose and Dosage Adjustment .......................................................... 5
- 4.4 Administration .......................................................................................................... 8
- 4.5 Missed Dose .................................................................................................................. 9
- 5 OVERDOSAGE ................................................................................................................ 9
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING .................................. 10
- 7
WARNINGS AND PRECAUTIONS ................................................................................... 10
- 7.1 Special Populations................................................................................................ 13
- 7.1.1 Pregnant Women .................................................................................................. 13
- 7.1.2 Breast-feeding ....................................................................................................... 13
- 7.1.3 Pediatrics ............................................................................................................... 13
- 7.1.4 Geriatrics ............................................................................................................... 13
- 8
ADVERSE REACTIONS ................................................................................................... 14
- 8.1 Adverse Reaction Overview................................................................................... 14
- 8.2 Clinical Trial Adverse Reactions ............................................................................. 14
8.5 Post-Market Adverse Reactions ............................................................................. 15
- 9
DRUG INTERACTIONS ................................................................................................... 16
- 9.1 Serious Drug Interactions ...................................................................................... 16
- 9.2 Drug Interactions Overview .................................................................................... 16
- 9.4 Drug-Drug Interactions .......................................................................................... 17
- 9.5 Drug-Food Interactions .......................................................................................... 18
- 9.6 Drug-Herb Interactions .......................................................................................... 18
- 9.7 Drug-Laboratory Test Interactions ......................................................................... 19
- 10
CLINICAL PHARMACOLOGY .......................................................................................... 19
- 10.1 Mechanism of Action ......................................................................................... 19
- 10.2 Pharmacodynamics ............................................................................................ 19
- 10.3 Pharmacokinetics ............................................................................................... 21
- 11 STORAGE, STABILITY AND DISPOSAL ............................................................................ 23
- 12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 23
PART II: SCIENTIFIC INFORMATION ......................................................................................... 24
- 13 PHARMACEUTICAL INFORMATION ............................................................................... 24
- 14
CLINICAL TRIALS ........................................................................................................... 23
- 14.1 Trial Design and Study Demographics ................................................................ 24
- 14.3 Comparative Bioavailability Study…………………………………………………………………….26
- 15 MICROBIOLOGY ........................................................................................................... 26
- 16 NON-CLINICAL TOXICOLOGY ........................................................................................ 27
- 17 SUPPORTING PRODUCT MONOGRAPHS ....................................................................... 29
PATIENT MEDICATION INFORMATION .................................................................................... 30
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
JAMP Ondansetron ODT (Ondansetron) is indicated for:
- the prevention of nausea and vomiting associated with mildly and moderately emetogenic chemotherapy and radiotherapy.
- the maintenance of antiemesis following intravenous doses of ondansetron used for the prevention of nausea and vomiting associated with highly emetogenic chemotherapy, including cisplatin.
- the prevention of post-operative nausea and vomiting.
- Pediatrics (<18 years of age)
Prevention of Nausea and Vomiting Associated with Mildly and Moderately Emetogenic Chemotherapy
- Pediatrics (4-12 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of JAMP Ondansetron ODT in pediatric patients 4-12 years of age has been established. Therefore, Health Canada has authorized an indication for pediatric use. (see 4.2 Recommended Dose and Dosage Adjustment, Pediatrics).
- Pediatrics (<4 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for the use of JAMP Ondansetron ODT in children less than 4 years of age.
Prevention of Nausea and Vomiting Associated with Radiotherapy
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for this use in any pediatric population.
Prevention of Post-Operative Nausea and Vomiting
No data are available to Health Canada; therefore, Health Canada has not authorized an indication for this use in any pediatric population.
- 1.2 Geriatrics
Prevention of Nausea and Vomiting Associated with Mildly and Moderately Emetogenic Chemotherapy, and Radiotherapy
Efficacy and tolerance of ondansetron were similar to that observed in younger adults. (See 4.2 Recommended Dose and Dosage Adjustment, Prevention of Less Emetogenic Chemotherapy
Induced Nausea and Vomiting, Geriatrics; 7 WARNINGS AND PRECAUTIONS, Cardiovascular; 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Geriatrics).
Prevention of Post-Operative Nausea and Vomiting
Clinical experience in the use of ondansetron in the prevention and treatment of post-operative nausea and vomiting in elderly patients is limited. Therefore, Health Canada has not authorized an indication for this use in the geriatric population.
2 CONTRAINDICATIONS
- JAMP Ondansetron ODT is contraindicated in patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- The concomitant use of apomorphine with JAMP Ondansetron ODT is contraindicated, based on reports of profound hypotension and loss of consciousness when apomorphine was administered with ondansetron (see 9.1 Serious Drug Interactions; 9.4 Drug-Drug Interactions).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- JAMP Ondansetron ODT (Ondansetron) is an orally disintegrating tablet. When injectable ondansetron is used, the product monograph for ondansetron hydrochloride dihydrate injection should be consulted.
- In patients with moderate or severe hepatic impairment, the total daily dose should not exceed 8 mg. (See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic).
- Exposure-response modelling predicted a greater effect on QTcF in patients ≥75 years of age compared to young adults. (See 10.3 Pharmacokinetics, Geriatrics).
Dosing considerations that reduce cardiac risks:
- Carefully follow the dosing guidelines.
- Use the minimum effective dose.
- Use oral ondansetron formulations, if possible (lower Cmax).
4.2 Recommended Dose and Dosage Adjustment
Prevention of Highly Emetogenic Chemotherapy Induced Nausea and Vomiting
Adults:
JAMP Ondansetron ODT is not indicated for this use.
Oral formulations of ondansetron, such as JAMP Ondansetron ODT, are not intended for the prevention of nausea and vomiting associated with highly emetogenic chemotherapy, such as cisplatin. An intravenous formulation should be given as an initial dose prior to chemotherapy and within the first 24 hours. Note: JAMP Ondansetron ODT is only available as oral disintegrating tablets. A product monograph for ondansetron hydrochloride injection should be consulted.
Pediatrics (<18 years):
Ondansetron is not indicated for this use in children.
Maintenance of Antiemesis Following Intravenous Doses of Ondansetron Used for the Prevention of Nausea and Vomiting Associated with Highly Emetogenic Chemotherapy
Adults:
For the maintenance of anti-emesis established by intravenous ondansetron:
- 8 mg orally every 8 hours, for up to 5 days; following the first 24 hours.
Pediatrics (<18 years of age):
JAMP Ondansetron ODT is not indicated for this use in children under 18 years of age.
Geriatrics:
Efficacy and tolerance in patients 65 years of age and older were similar to that seen in younger adults. No dosage adjustment is required in this population (see 7.1.4 Geriatrics; 10.3 Pharmacokinetics, Geriatrics).
Hepatic Insufficiency:
No dosage adjustment is needed in patients with mild hepatic impairment.
In patients with moderate or severe hepatic impairment (Child-Pugh score ≥ 7), do not exceed a total daily dose of 8 mg (Child-Pugh score of 10 or greater) (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics). This may be given as a single oral dose.
Renal Insufficiency:
No alteration of daily dosage, frequency of dosing, or route of administration is required in patients with impaired renal function (see 10.3 Pharmacokinetics, Renal Insufficiency).
Prevention Of Nausea And Vomiting Associated With Mildly And Moderately Emetogenic Chemotherapy
Adults:
- 8 mg orally, 1 - 2 hours prior to chemotherapy, followed by 8 mg orally, twice daily for up to 5 days.
Pediatrics (4-18 years of age):
Following chemotherapy*: 4 mg orally, every 8 hours, for up to 5 days.
*For prevention of chemotherapy induced nausea and vomiting in children 4-18 years of age, intravenous ondansetron should be administered 30 minutes before chemotherapy. Note: JAMP Ondansetron ODT is only available as orally disintegrating tablet. A product monograph for ondansetron hydrochloride injection should be consulted.
Pediatrics (<4 years of age):
JAMP Ondansetron ODT is not indicated for this use in children under 4 years of age.
Geriatrics:
Efficacy and tolerance in patients 65 years of age and older were similar to that seen in younger adults indicating no need to alter dosage schedules in this population (see 10.3 Pharmacokinetics, Geriatrics).
Hepatic Insufficiency:
No dosage adjustment is needed in patients with mild hepatic impairment.
In patients with moderate or severe hepatic impairment (Child-Pugh score ≥ 7), do not exceed a total daily dose of 8 mg (Child-Pugh score of 10 or greater) (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics). This may be given as a single oral dose.
Renal Insufficiency:
No alteration of daily dosage, frequency of dosing, or route of administration is required in patients with impaired renal function (see 10.4 Pharmacokinetics, Renal Insufficiency).
Prevention of Radiotherapy Induced Nausea and Vomiting
Adults:
- 8 mg orally, given 1 - 2 hours before radiotherapy followed by 8 mg orally, given every 8 hours, for up to 5 days after a course of treatment.
Pediatrics (<18 years of age):
JAMP Ondansetron ODT is not indicated for this use in the pediatric population.
Geriatrics:
Efficacy and tolerance in patients 65 years of age and older were similar to that seen in younger adults, indicating no need to alter dosage schedules in this population (see 4.2 Adults, and 4.1 Dosing Considerations; 10.3 Pharmacokinetics, Geriatrics).
Hepatic Insufficiency:
No dosage adjustment is needed in patients with mild hepatic impairment.
In patients with moderate or severe hepatic impairment (Child-Pugh score ≥ 7), do not exceed a total daily dose of 8 mg (Child-Pugh score of 10 or greater) (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics). This may be given as a single oral dose.
Renal Insufficiency:
No alteration of daily dosage, frequency of dosing, or route of administration is required in patients with impaired renal function (see 10.4 Pharmacokinetics, Renal Insufficiency).
Prevention of Post-Operative Nausea and Vomiting
Adults:
- 16 mg orally, administered 1 hour prior to induction of anaesthesia
Pediatrics (<18 years of age):
JAMP Ondansetron ODT is not indicated for this use in the pediatric population.
Geriatrics:
JAMP Ondansetron ODT is not indicated for this use in patients 65 years of age and older.
Hepatic Insufficiency:
No dosage adjustment is needed in patients with mild hepatic impairment.
In patients with moderate or severe hepatic impairment (Child-Pugh score ≥ 7), do not exceed a total daily dose of 8 mg (Child-Pugh score of 10 or greater) (see 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic; 10.3 Pharmacokinetics). This may be given as a single oral dose.
Renal Insufficiency:
No adjustment of daily dosage, frequency of dosing, or route of administration is required in patients with impaired renal function (see 10.4 Pharmacokinetics, Renal Insufficiency).
4.4 Administration
Patient instructions:
- Do not try to push JAMP Ondansetron ODT out through the foil backing on the blister pocket.
- Just prior to use, with dry fingers, carefully peel back the foil backing where indicated by the arrow. Gently push the tablet out of the blister pocket.
- Immediately place the JAMP Ondansetron ODT tablet on top of the tongue. It will disperse within seconds, then swallow as normal.
4.5 Missed Dose
If a dose is missed, it should be taken as soon as possible. However, if it is almost time for the next dose, the missed dose should be skipped and the patient returned to their regular dosing schedule. Do not double doses.
If a dose is missed, and the patient feels nauseated or vomits, the missed dose should be taken as soon as possible.
If a dose of JAMP Ondansetron ODT is vomited, do not repeat the dose. JAMP Ondansetron ODT is rapidly absorbed.
5 OVERDOSAGE
At present there is little information concerning overdosage with ondansetron. Individual doses of 84 mg and 145 mg and total daily doses as large as 252 mg have been administered with only mild side effects. There is no specific antidote for ondansetron, therefore, in cases of suspected overdosage, symptomatic and supportive therapy should be given as appropriate.
The use of Ipecac to treat overdosage with ondansetron is not recommended as patients are unlikely to respond due to the antiemetic action of ondansetron itself.
“Sudden blindness” (amaurosis) of 2 to 3 minutes duration plus severe constipation occurred in one patient that was administered 72 mg of ondansetron intravenously as a single dose.
Hypotension (and faintness) occurred in another patient that took 48 mg of oral ondansetron. Following infusion of 32 mg over only a 4-minute period, a vasovagal episode with transient second-degree heart block was observed. Neuromuscular abnormalities, autonomic instability, somnolence, and a brief generalized tonic-clonic seizure (which resolved after a dose of benzodiazepine) were observed in a 12 months’ old infant who ingested seven or eight 8-mg ondansetron tablets (approximately forty times the recommended 0.1-0.15 mg/kg dose for a pediatric patient). In all instances, the events resolved completely.
Ondansetron prolongs QT interval in a dose-dependent fashion (see 10.2 Pharmacodynamics). ECG monitoring is recommended in cases of overdose.
Cases consistent with serotonin syndrome have been reported in young children following oral overdose (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome).
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada's toll-free number, 1-844 POISON-X
(1-844-764-7669).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1 – Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | ODT Orally disintegrating tablets/ 4 mg and 8 mg ondansetron (base) | Aspartame (see 7 WARNINGS AND PRECAUTIONS, General), colloidal silicon dioxide, crospovidone, lactose monohydrate, magnesium stearate, mannitol, microcrystalline cellulose, and strawberry flavour (contains acacia gum, nature-identical flavouring substances, sugar, and tapioca maltodextrin). |
4 mg: White to off-white, round, flat beveled edged tablets debossed with "4" on one side and plain on the other side, having strawberry odour.
8 mg: White to off-white, round, flat beveled edged tablets debossed with "8" on one side and plain on the other side, having strawberry odour.
JAMP Ondansetron ODT orally disintegrating tablets are packaged in blister pack of 10’s count with a peelable, foil laminate lidding.
JAMP Ondansetron ODT (ondansetron orally disintegrating tablets, USP) meets USP Disintegration Test 2.
7 WARNINGS AND PRECAUTIONS
General
JAMP Ondansetron ODT is not effective in preventing motion-induced nausea and vomiting.
Cardiovascular
QTc Interval Prolongation
Ondansetron prolongs the QT interval (see 10.2 Pharmacodynamics, Electrocardiography). The magnitude of QTc prolongation will depend on the peak serum ondansetron concentration (Cmax), which is substantially determined by the route of administration, the dose and the infusion rate of intravenous ondansetron. In addition, post-marketing cases of torsade de pointes have been reported in patients using ondansetron. Torsade de pointes is a polymorphic ventricular tachyarrhythmia. Generally, the risk of torsade de pointes increases with the magnitude of QTc prolongation produced by the drug. Torsade de pointes may be asymptomatic or experienced by the patient as dizziness, palpitations, syncope, or seizures. If sustained, torsade de pointes can progress to ventricular fibrillation and sudden cardiac death.
Avoid ondansetron in patients with congenital long QT syndrome. Ondansetron should be administered with caution to patients who have or may develop prolongation of QTc, including congestive heart failure, bradyarrhythmia’s or patients taking other medicinal products that lead to either QT prolongation or electrolyte abnormalities (see 9.4Drug-Drug Interactions).
Hypokalemia, hypocalcemia and hypomagnesemia should be corrected prior to ondansetron administration.
Additional risk factors for torsade de pointes in the general population include, but are not limited to, the following:
- female gender;
- age 65 years or older;
- baseline prolongation of the QT/QTc interval;
- presence of genetic variants affecting cardiac ion channels or regulatory proteins;
- family history of sudden cardiac death at <50 years;
- cardiac disease (e.g., myocardial ischemia or infarction, left ventricular hypertrophy, cardiomyopathy, conduction system disease);
- history of arrhythmias (especially ventricular arrhythmias, atrial fibrillation, or recent conversion from atrial fibrillation);
- bradycardia (<50 beats per minute);
- acute neurological events (e.g., intracranial or subarachnoid hemorrhage, stroke, intracranial trauma);
- nutritional deficits (e.g., eating disorders, extreme diets);
- diabetes mellitus;
- autonomic neuropathy.
Myocardial Ischemia and Coronary Artery Spasm
Ondansetron can cause coronary artery vasospasm, and myocardial ischemia, which may lead to myocardial infarction. In some cases, the symptoms appeared immediately after IV infusion, or shortly after oral administration, including after low doses in patients without significant known pre-existing cardiovascular disease or other risk factors. Caution is advised during and after ondansetron administration, and close monitoring is recommended in patients with known or suspected ischemic or vasospastic coronary artery disease or other significant underlying cardiovascular disease.
Driving and Operating Machinery
In psychomotor testing ondansetron does not impair performance or cause sedation.
Endocrine and Metabolism
Phenylketonuria
JAMP Ondansetron ODT (ondansetron) contains aspartame. Exercise caution when using JAMP Ondansetron ODT in patients with phenylketonuria.
Gastrointestinal
As ondansetron is known to increase large bowel transit time, patients with signs of subacute intestinal obstruction should be monitored following administration of JAMP Ondansetron ODT.
Hepatic/Biliary/Pancreatic
Abnormal liver function test results have been reported, as well as liver failure in clinical trial cancer patients. (See 8.2 Clinical Trial Adverse Reactions, Hepatic/Biliary/Pancreatic and 8.5 Post-Market Adverse Reactions).
Immune
Cross-reactive hypersensitivity has been reported between different 5-HT3 antagonists. Patients who have experienced hypersensitivity reactions to one 5-HT3 antagonist have experienced more severe reactions upon being challenged with another drug of the same class. The use of a different 5-HT3 receptor antagonist is not recommended as a replacement in cases in which a patient has experienced even a mild hypersensitivity type reaction to another 5-HT3 antagonist.
Neurologic
Serotonin Toxicity /Neuroleptic Malignant Syndrome
On rare occasions, serotonin toxicity, also known as serotonin syndrome, has been reported with ondansetron, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature > 38°C and ocular clonus or inducible clonus
Neuroleptic malignant syndrome has also been rarely reported with ondansetron, particularly during combined use with neuroleptic/antipsychotic drugs. The clinical manifestations of neuroleptic malignant syndrome often overlap with those of serotonin toxicity, including hyperthermia, hypertonia, altered mental status, and autonomic instability. In contrast to serotonin toxicity, patients with neuroleptic malignant syndrome may present with “lead pipe” muscle rigidity as well as hyporeflexia.
Ondansetron should be used with caution in patients receiving other serotonergic drugs or antipsychotics/neuroleptics. If concomitant treatment with ondansetron, and other serotonergic drugs and/or antipsychotics/neuroleptics is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). Serotonin toxicity and neuroleptic malignant syndrome may result in potentially life-threatening conditions. If serotonin toxicity or neuroleptic malignant syndrome is suspected, discontinuation of JAMP Ondansetron ODT, should be considered.
Reproductive Health: Female and Male Potential
Pregnancy status should be verified for females of reproductive potential prior to starting treatment with JAMP Ondansetron ODT.
Females of reproductive potential should be advised of the possible harm that JAMP Ondansetron ODT can cause harm to the developing foetus (see 7.1.1 Pregnant Women). Sexually active females of reproductive potential should use effective contraception (methods that result in less than 1% pregnancy rates) when using JAMP Ondansetron ODT and for two days after stopping treatment with JAMP Ondansetron ODT.
7.1 Special Populations
7.1.1 Pregnant Women
The use of ondansetron during pregnancy is not recommended.
Ondansetron use during early pregnancy has been associated with a small increase in orofacial malformations. Despite some limitations in methodology, several human epidemiological studies have noted an increase in orofacial clefts in infants of women administered ondansetron during the first trimester of pregnancy. Regarding cardiac malformations, the epidemiological studies showed conflicting results.
Ondansetron is not teratogenic in animals (see 16 NON- CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
7.1.2 Breast-feeding
Ondansetron is excreted in the milk of lactating rats. It is not known if it is excreted in human milk. However, breast-feeding is not recommended during treatment with ondansetron.
7.1.3 Pediatrics
Insufficient information is available to inform dosage recommendations for children 3 years of age or younger. JAMP Ondansetron ODT is not indicated for use in children less than 4 years of age (see 1.1 Pediatrics).
7.1.4 Geriatrics
Early Phase I studies in healthy elderly volunteers showed a slight age-related decrease in clearance, and an increase in half-life of ondansetron. A greater effect on QTcF is predicted in patients ≥75 years of age compared to young adults, based on exposure-response modelling. See 10.3 Pharmacokinetics, Geriatrics.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most frequent adverse events reported in controlled clinical trials were headache (11%) and constipation (4%). Other adverse events include sensations of flushing or warmth (< 1%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Ondansetron has been administered to over 2500 patients worldwide in controlled clinical trials and has been well tolerated.
Cardiovascular:
There have been rare reports of tachycardia, angina (chest pain), bradycardia, hypotension, syncope and electrocardiographic alterations.
Central Nervous System:
There have been rare reports of seizures. Movement disorders and dyskinesia have been reported in two large clinical trials of ondansetron at a rate of 0.1 – 0.3%.
Dermatological:
Rash has occurred in approximately 1% of patients receiving ondansetron.
Eye Disorder:
There have been reports of transient visual disturbances, including blurred vision and, in very rare cases, transient blindness, during or shortly after ondansetron treatment. These were observed generally within the recommended dosing range and predominantly during intravenous administration. The majority of blindness cases resolved within 20 minutes.
Hepatic/Biliary/Pancreatic:
There were transient increases of SGOT and SGPT of over twice the upper limit of normal in approximately 5% of patients. These increases did not appear to be related to dose or duration of therapy. There have been reports of liver failure and death in patients with cancer receiving concurrent medications including potentially hepatotoxic cytotoxic chemotherapy and antibiotics. The etiology of the liver failure is unclear.
Hypersensitivity:
Rare cases of immediate hypersensitivity reactions sometimes severe, including anaphylaxis, bronchospasm, urticaria and angioedema have been reported.
Metabolic:
There have been rare reports of hypokalemia.
Other:
There have been reports of abdominal pain, weakness and xerostomia.
8.5 Post-Market Adverse Reactions
Over 250 million patient treatment days of ondansetron have been supplied since the launch of the product worldwide. The following events have been spontaneously reported during post- approval use of ondansetron, although the link to ondansetron cannot always be clearly established.
The adverse event profiles in children and adolescents were comparable to that seen in adults.
Cardiovascular Disorders:
There have been rare reports (< 0.01%) of myocardial infarction, myocardial ischemia, angina, chest pain with or without ST segment depression, arrhythmias (including ventricular or supraventricular tachycardia, premature ventricular contractions, and atrial fibrillation), electrocardiographic alterations (including second degree heart block), palpitations and syncope.
Rarely and predominantly with intravenous ondansetron, transient ECG changes including QTc interval prolongation, Torsade de Pointes, ventricular fibrillation, coronary artery spasm, myocardial ischemia, cardiac arrest, and sudden death have been reported (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular).
Eye Disorder:
There have been very rare cases of transient blindness following ondansetron treatment, generally within the recommended dosing range and predominantly during intravenous administration.
The majority of blindness cases reported resolved within 20 minutes. Although most patients had received chemotherapeutic agents, including cisplatin a few cases of transient blindness occurred following ondansetron administration for the treatment of post-operative nausea or vomiting and in the absence of cisplatin treatment. Some cases of transient blindness were reported as cortical in origin.
Hepatic/Biliary/Pancreatic:
Occasional asymptomatic increases in liver function tests have been reported.
Immune Disorders:
Rare cases of hypersensitivity reactions, sometimes severe (e.g., laryngeal oedema, stridor, laryngospasm and cardiopulmonary arrest) have also been reported.
Nervous System Disorders:
Transient episodes of dizziness (<0.1%) have been reported predominantly during or upon completion of IV infusion of ondansetron.
Uncommon reports (<1%) suggestive of extrapyramidal reactions including oculogyric crisis/dystonic reactions (e.g. oro-facial dyskinesia, opisthotonos, tremor, etc.), movement disorders and dyskinesia have been reported without definitive evidence of persistent clinical sequelae.
Serotonin syndrome and neuroleptic malignant syndrome-like events have been reported with 5-HT3 receptor antagonist antiemetics, including ondansetron, when given in combination with other serotonergic and/or neuroleptic drugs (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
Respiratory, Thoracic and Mediastinal Disorders:
There have also been rare reports of hiccups.
Skin and Subcutaneous Tissue Disorders:
Very rare reports have been received for bullous skin and mucosal reactions, including fatal cases. These reports include toxic skin eruptions such as Stevens-Johnson syndrome and toxic epidermal necrolysis, and have occurred in patients taking other medications that can be associated with bullous skin and mucosal reactions.
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
Serious Drug Interactions (see 9.4 Drug-Drug Interactions)
|
|---|
9.2 Drug Interactions Overview
Ondansetron is extensively metabolised by multiple hepatic cytochrome P450 enzymes: (predominately CYP3A4, also CYP2D6 and CYP1A2), and clearance is reduced in hepatic insufficiency (see 10.3 Pharmacokinetics, Hepatic Insufficiency).
CYP 3A4 inducers can increase ondansetron clearance (see 9.4. Drug-Drug Interactions, CYP
3A4 Inducers).
Ondansetron does not, itself, appear to induce or inhibit the cytochrome P450 drug metabolizing enzyme system of the liver.
9.3 Drug-Behavioural Interactions
Potential interactions, in terms of individual behavioural risks, have not been established.
9.4 Drug-Drug Interactions
CYP 3A4 inducers
Patients treated with inducers of CYP3A4 (i.e. phenytoin, carbamazepine, and rifampicin) demonstrated an increase in clearance of oral ondansetron and a decrease in ondansetron blood concentrations.
In a pharmacokinetic study of 16 epileptic patients maintained chronically on carbamazepine or phenytoin (CYP 3A4 inducers), reduction in AUC, Cmax and T½ of ondansetron was observed.
This resulted in a significant increase in clearance. However, no dosage adjustment can be recommended, due to inter-subject variability in the available data.
Cytochrome P450 Inhibitors
No effect on ondansetron clearance secondary to enzyme inhibition or reduced activity (e.g. CYP2D6 genetic deficiency) has been identified, to date.
QTc-Prolonging Drugs
The concomitant use of JAMP Ondansetron ODT with another QTc- prolonging drug should be carefully considered to determine that the therapeutic benefit outweighs the potential risk (see 7 WARNINGS AND PRECAUTIONS, Cardiovascular; 9.1 Serious Drug Interactions). Drugs that have been associated with QTc interval prolongation and/or torsade de pointes include, but are not limited to, the examples in the following list. Chemical/pharmacological classes are listed if some, although not necessarily all, class members have been implicated in QTc prolongation and / or torsade de pointes:
- Class IA antiarrhythmics (e.g. quinidine, procainamide, disopyramide)
- Class III antiarrhythmics (e.g. amiodarone, sotalol, ibutilide, dronedarone)
- Class 1C antiarrhythmics (e.g. flecainide, propafenone)
- antiemetics (e.g. dolasetron, palonosetron, granisetron, droperidol, chlorpromazine, prochlorperazine)
- tyrosine kinase inhibitors (e.g. vandetanib, sunitinib, nilotinib, lapatinib)
- antipsychotics (e.g. chlorpromazine, pimozide, haloperidol, ziprasidone)
- antidepressants (e.g. citalopram, fluoxetine, venlafaxine, tricyclic/tetracyclic, amitriptyline, imipramine, maprotiline)
- opioids (e.g., methadone)
- domperidone
- macrolide antibiotics and analogues (e.g. erythromycin, clarithromycin, telithromycin, tacrolimus)
- quinolone antibiotics (e.g. moxifloxacin, levofloxacin, ciprofloxacin)
- antimalarials (e.g. quinine, chloroquine)
- azole antifungals (e.g. ketoconazole, fluconazole, voriconazole)
- histone deacetylase inhibitors (e.g. vorinostat)
- beta-2 adrenoceptor agonists (e.g. salmeterol, formoterol).
Drugs that Cause Electrolyte Abnormalities: The use of ondansetron orally disintegrating tablets with drugs that can disrupt electrolyte levels should be avoided. Such drugs include, but are not limited to, the following:
- loop, thiazide, other related diuretics
- laxatives and enemas
- amphotericin B
- high dose corticosteroids
Tramadol
Data from small studies indicate that ondansetron may reduce the analgesic effect of tramadol.
Apomorphine
Based on reports of profound hypotension and loss of consciousness when ondansetron was administered with apomorphine hydrochloride, concomitant use with apomorphine is contraindicated (see 2 CONTRAINDICATIONS; 9.1 Serious Drug Interactions).
Serotonergic Drugs
As with other serotonergic agents, serotonin syndrome/toxicity, a potentially life - threatening condition, may occur with 5-HT3 receptor antagonist antiemetic treatment when given in combination with other agents that may affect the serotonergic neurotransmitter system, including triptans, selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), other 5-HT3 receptor antagonists, lithium, sibutramine, fentanyl and its analogues, dextromethorphan, tramadol, tapentadol, meperidine, methadone, pertazocine, St. John’s Wort (Hypericum perforatum)] and MAOIS, including phenelzine, moclobemide, tranylcypromine, linezolid (an antibiotic which is a reversible non-selective MAOI) and methylene blue (see 7 WARNINGS AND PRECAUTIONS, Neurologic; 9.1 Serious Drug Interactions).
Antipsychotics/Neuroleptics
Neuroleptic malignant syndrome has been rarely reported with ondansetron, particularly during combined use with neuroleptic/antipsychotic drugs (e.g. haloperidol, olanzapine, quetiapine, risperidone) (see 7 WARNINGS AND PRECAUTIONS, Neurologic).
The above list of potential drug interactions is not comprehensive. Current information sources should be consulted for newly approved drugs that prolong the QTc interval, affect the serotonergic system, increase CYP 3A4 enzyme activity, or cause electrolyte disturbances, as well as for older drugs for which these effects have recently been established.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
Exercise caution when using JAMP Ondansetron ODT with herbal products that may alter serotonin levels or act as CYP3A4 inducers/inhibitors, such as St. John’s wort, ginseng, L-tryptophan, valerian, and Ginkgo biloba.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Ondansetron is a selective antagonist of the serotonin receptor subtype, 5-HT3. Its precise mode of action in the control of chemotherapy induced nausea and vomiting is not known.
Cytotoxic chemotherapy and radiotherapy are associated with the release of serotonin
(5-HT) from enterochromaffin cells of the small intestine, presumably initiating a vomiting reflex through stimulation of 5-HT3 receptors located on vagal afferents. Ondansetron may block the initiation of this reflex. Activation of vagal afferents may also cause a central release of serotonin from the chemoreceptor trigger zone of the area postrema, located on the floor of the fourth ventricle. Thus, the antiemetic effect of ondansetron is probably due to the selective antagonism of 5-HT3 receptors on neurons located in either the peripheral or central nervous systems, or both.
The mechanisms of ondansetron's antiemetic action in post-operative nausea and vomiting are not known.
10.2 Pharmacodynamics
Serotonin receptors of the 5-HT3 type are present both peripherally and on vagal nerve terminals. Ondansetron probably acts by preventing activation of these receptors or receptors located in other regions of the central nervous system. Both the peripheral and central nervous systems appear to be involved since both abdominal vagotomy and microinjection of ondansetron and other 5-HT3 antagonists directly into the area postrema eliminate cisplatin- induced emesis, while 5-HT1-like (methiothepin maleate) and 5-HT2 (ketanserin) antagonists have no effect.
Ondansetron is highly selective for 5-HT3 receptors and shows negligible binding to other receptors such as 5-HT1-like, 5-HT2, α1 and α2 adrenoceptors, β1 and β2 adrenoceptors, D1 and D2 muscarinic, nicotinic, GABAA, H1 and H2 receptors.
The pharmacological specificity of ondansetron may explain the observed lack of extrapyramidal side effects often seen following similar therapy with metoclopramide, which preferentially binds to dopamine receptors of the D2 subtype.
In vivo pharmacodynamic studies have investigated the effects of ondansetron on gastric emptying, small bowel transit time and oesophageal motility.
Both oral (16 mg tid) and intravenous (5-10 mg) doses of ondansetron failed to produce a significant effect on gastric emptying in both healthy volunteers and in patients suffering from delayed gastric emptying. However, in one study intravenous doses of 8 mg did increase gastric emptying in over half the volunteers tested.
Intravenous infusion of either 1 mg or 5 mg ondansetron tended to increase small bowel transit times and single intravenous doses of 10 mg ondansetron have been reported to decrease sphincter pressure in the lower oesophagus in some subjects.
Electrocardiography
A study in cloned human cardiac ion channels has shown ondansetron has the potential to affect cardiac repolarisation via blockade of hERG potassium channels at clinically relevant concentrations. Dose-dependent QT prolongation has been observed in a thorough QT study in human volunteers.
The effect of ondansetron on the QTc interval was evaluated in a double blind, randomized, placebo and positive (moxifloxacin) controlled, crossover study in 58 healthy adult men and women. Ondansetron was tested at single doses of 8 mg and 32 mg infused intravenously over 15 minutes. At the highest tested dose of 32 mg, prolongation of the Fridericia-corrected QTc interval (QT/RR0.33=QTcF) was observed from 15 min to 4 h after the start of the 15 min infusion, with a maximum mean (upper limit of 90% CI) difference in QTcF from placebo after baseline-correction of 19.6 (21.5) msec at 20 min. At the lower tested dose of 8 mg, QTc prolongation was observed from 15 min to 1 h after the start of the 15 minute infusion, with a maximum mean (upper limit of 90% CI) difference in QTcF from placebo after baseline - correction of 5.8 (7.8) msec at 15 min. The magnitude of QTc prolongation with ondansetron is expected to be greater if the infusion rate is faster than 15 minutes. The 32 mg intravenous dose of ondansetron must not be administered.
No treatment-related effects on the QRS duration or the PR interval were observed at either the 8 or 32 mg dose.
Figure 1: LS Mean Difference (90% CI) in QTcF Interval Between Treatment and Placebo Over Time
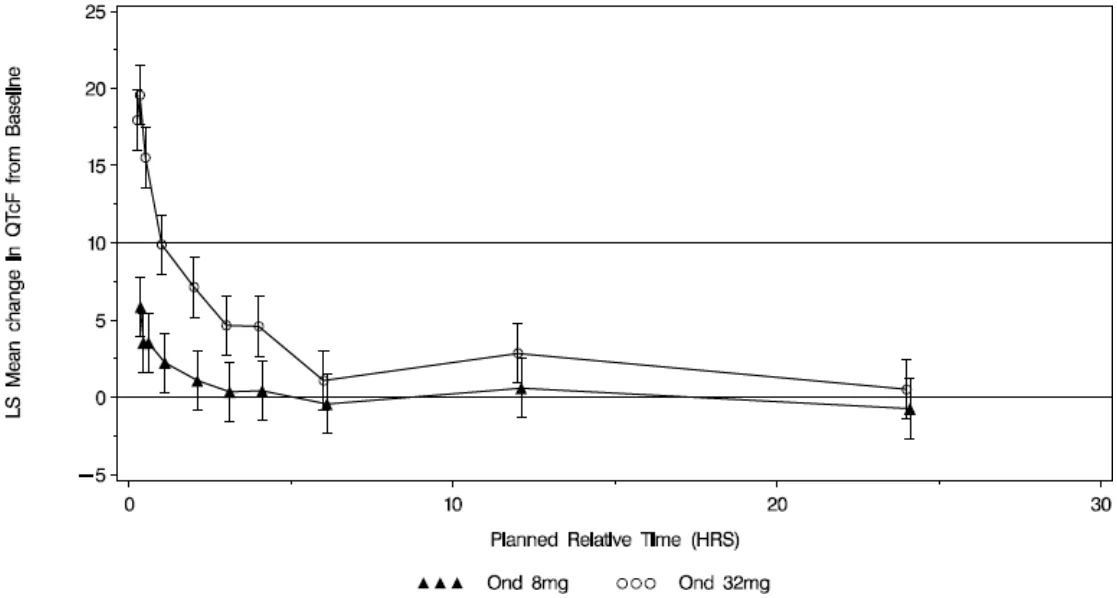
An ECG assessment study has not been performed for orally administered ondansetron. On the basis of pharmacokinetic-pharmacodynamic modelling, an 8 mg oral dose of ondansetron is predicted to cause a mean QTcF increase of 0.7 ms (90% CI -2.1, 3.3) at steady-state, assuming a mean maximal plasma concentration of 24.7 ng/mL (95% CI 21.1, 29.0).
The magnitude of QTc prolongation at the recommended 5 mg/m2 dose in pediatrics has not been studied, but pharmacokinetic-pharmacodynamic modelling predicts a mean increase of
6.6 ms (90% CI 2.8, 10.7) at maximal plasma concentrations.
- 10.3 Pharmacokinetics
Absorption
Pharmacokinetic studies in human volunteers showed peak plasma levels of 20-30 ng/mL at around 1½ hours after an 8 mg oral dose of ondansetron. Repeat dosing of an 8 mg tablet every 8 hours for 6 days increased the peak plasma value to 40 ng / mL.
Distribution
The absolute bioavailability of ondansetron in humans was approximately 60% and the plasma protein binding was approximately 73%.
Metabolism
In vitro metabolism studies have shown that ondansetron is a substrate for human hepatic cytochrome P450 enzymes, including CYP1A2, CYP2D6 and CYP3A4. In terms of overall ondansetron turnover, CYP3A4 played the predominant role. Because of the multiplicity of metabolic enzymes capable of metabolising ondansetron, it is likely that inhibition or loss of one enzyme (e.g. CYP2D6 enzyme deficiency) will be compensated by others and may result in little change in overall rates of ondansetron clearance. CYP 3A4 inducers can increase clearance (see 9.4 Drug-Drug Interactions, CYP 3A4 inducers).
Elimination
Following extensive metabolism of an orally or intravenously administered dose, ondansetron is excreted in the urine and feces. In humans, less than 10% of the dose is excreted unchanged in the urine. The major urinary metabolites are glucuronide conjugates (45%), sulphate conjugates (20%) and hydroxylation products (10%).
The half-life of ondansetron after either an 8 mg oral dose or intravenous dose was approximately 3-4 hours and may be extended to 6-8 hours in the elderly.
Special Populations and Conditions
- Geriatrics
Early Phase I studies in healthy elderly volunteers showed a slight age-related decrease in clearance, and an increase in half-life of ondansetron. However, wide inter-subject variability resulted in considerable overlap in pharmacokinetic parameters between young (< 65 years of age) and elderly subjects (≥ 65 years of age) and there were no overall differences in safety or efficacy observed between young and elderly cancer patients enrolled in CINV clinical trials. (See 4.2 Recommended Dose and Dosage Adjustment, Geriatrics). There is limited data involving patients ≥75 years of age. Based on more recent ondansetron plasma concentrations and exposure-response modelling, a greater effect on QTcF is predicted in patients ≥75 years of age compared to young adults (see 4.2 Recommended Dose and Dosage Adjustment).
- Genetic Polymorphism
CYP 2D6: The elimination half-life and plasma levels of a single 8 mg intravenous dose of ondansetron did not differ between subjects classified as poor and extensive metabolisers of sparteine and debrisoquine (CYP 2D6 substrates). No alteration of daily dosage or frequency of ondansetron dosing is recommended for patients known to be CYP 2D6 poor metabolisers.
- Hepatic Insufficiency
Ondansetron is extensively metabolized by the liver. The clearance of an 8 mg intravenous dose of ondansetron was significantly reduced and the serum half-life significantly prolonged in subjects with severe impairment of hepatic function. In patients with moderate or severe impairment of hepatic function, reductions in dosage are therefore recommended (see 4.2 Recommended Dose and Dosage Adjustment).
There is no experience in patients who are clinically jaundiced.
- Renal Insufficiency
Renal impairment is not expected to significantly influence the total clearance of ondansetron, as renal clearance represents only 5% of the overall clearance. No dosage adjustment is required in patients with impaired renal function (see 4.2 Recommended Dose and Dosage Adjustment).
11 STORAGE, STABILITY AND DISPOSAL
JAMP Ondansetron ODT (ondansetron) orally disintegrating tablets should be stored between 15-30°C. Keep in a safe place out of reach and sight of children. There is no specific instructions for disposal.
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this drug product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: ondansetron
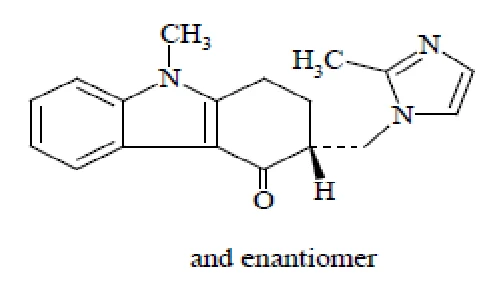
Chemical name: 4H-Carbazol-4-one, 1,2,3,9-tetrahydro-9-methyl-3-[(2-methyl-1H-imidazol-1-yl)methyl]- (±)-.
Molecular formula and molecular mass: C18H19N3O, 293.36 g/mol
Structural formula:
Physicochemical properties:
Description and Solubility:
Ondansetron is a white to off-white powder. It is very soluble in acetic acid solution. It is very slightly soluble at pH 1.68, slightly soluble at pH 4.01, practically insoluble at pH 6.86, 9.18 and 12.45.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
The clinical trial data on which the original indication was authorized is not available.
Clinical trial results showing the number and percentage of patients exhibiting a complete response to ondansetron (0 emetic episodes) are shown in the tables below for both post- operative and chemotherapy induced emesis.
Prevention of Chemotherapy Induced Emesis
Table 2 - Prevention of Chemotherapy Induced Emesis - Response Over 24 Hours*
| Dose | ondansetron 3 oral doses of 0.15 mg/kg | Placebo 3 oral doses of placebo |
|---|---|---|
| # of patients | 14 | 14 |
Treatment Response: 0 emetic episodes 1-2 emetic episodes | 2 (14%) 8 (57%) | 0 (0%) 0 (0%) |
*Results are from an initial study using a different dosing regimen.
Prevention of Post-Operative Emesis
Table 3 - Prevention of Post-Operative Emesis – Response Over 24 Hours*
| Oral Prevention | ||||
|---|---|---|---|---|
| Dose | ondansetron 16 mg od | Placebo | p value | |
| # of patients | 253 | 250 | ||
Treatment Response: 0 emetic episodes | 126 (50%) | 79 (32%) | < 0.001 | |
* The majority of patients included in the prevention and treatment of post-operative nausea and vomiting studies using ondansetron have been adult women receiving balanced anaesthesia for gynaecological surgery.
Prevention of Radiotherapy Induced Emesis
Table 4 - Prevention of Radiotherapy Induced Emesis – Response Over 24 Hours*
| Oral Treatment | |||
|---|---|---|---|
| Dose | ondansetron 8 mg PO tid* | Metoclopramide 10 mg PO tid* | p value |
| # of patients | 38 | 44 | |
Treatment Response: 0 emetic episodes | 37 (97%) | 20 (45%) | < 0.001 |
*results from a study of adult male and female patients receiving single high dose radiotherapy (800 to 1,000 cGy) over an anterior or posterior field size of ≥ 80 cm2 to the abdomen.
*Patients received the first dose of ondansetron 8 mg tablets or metoclopramide (10 mg) 1-2 hours before radiotherapy. If radiotherapy was given in the morning, 2 additional doses of study treatment were given (1 tablet late afternoon and 1 tablet before bedtime). If radiotherapy was given in the afternoon, patients took only 1 further tablet that day before bedtime. Patients continued oral medication on a 3 times a day basis for 3-5 days.
14.3 Comparative Bioavailability Study
A double blinded, balanced, randomized, two treatment, two sequence, two period, two way crossover, single oral dose bioequivalence study of JAMP Ondansetron ODT, 8 mg tablets
(JAMP Pharma Corporation), and PrONDANSETRON ODT, 8 mg tablets (Sandoz Canada Inc.) was conducted in healthy, adult, male subjects under fasting condition. Comparative bioavailability data from 28 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Ondansetron (1 X 8 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90 % Confidence Interval |
AUCT (ng.h /mL) | 263.08 288.49 (42.16) | 270.69 295.70 (38.29) | 97.2 | 90.0 - 105.0 |
AUCI (ng.h /mL) | 277.41 304.92 (42.87) | 285.24 312.71 (39.65) | 97.3 | 89.8 - 105.3 |
Cmax (ng/mL) | 36.74 39.26 (36.64) | 40.28 43.27 (36.20) | 91.2 | 83.7 - 99.4 |
Tmax3 (h) | 2.17 (1.00 - 4.00) | 1.75 (0.50 - 3.00) | ||
T½4 (h) | 5.04 (19.38) | 5.11 (26.04) | ||
1 JAMP Ondansetron ODT (ondansetron) 8 mg tablets (JAMP Pharma Corporation)
2 PrONDANSETRON ODT (ondansetron), 8 mg tablets (Sandoz Canada Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
No microbiological information is required for this product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
- Acute Toxicity
Single doses of ondansetron up to the LD50 in mice and in rats were generally well tolerated. Reactions, including tremor and convulsive behavior, occurred only at near lethal levels.
Table 5 – Acute Toxicity
| Species | LD50 (mg/kg) |
|---|---|
| Mice Rats | Oral |
10-30 100-150 |
All deaths resulted from the acute effects of treatment, the observed clinical signs being consistent with the central nervous system effects associated with behavioral depression. These effects were not associated with any apparent histopathological changes in the brain. No target organ toxicity was identified.
- Long-term Toxicity
Table 6 - Subacute Toxicity Studies
| Species | Route | Dose (mg/kg/day) | Duration of Study | Results |
|---|---|---|---|---|
Rats Dogs | Oral IV Oral IV | 160 12 7.5-25 2-8 | 7 weeks 5 weeks 5 weeks 5 weeks | Well tolerated Well tolerated Transient post-dosing clinical reactions associated with behavioral depression (at highest dose levels) |
Maximum daily dose levels in rats were found to be higher when doses were gradually increased. Identical doses were rapidly lethal to rats not previously exposed to ondansetron. Post-dosing reactions, in both rats and dogs, included ataxia, exophthalmia, mydriasis, tremor and respiratory changes. Increases in liver enzymes (SGPT and SGOT) were noted at high dose levels. Dogs dosed at 6.75 mg/kg/day intravenously exhibited vein irritancy in the form of constriction and thickening, creating resistance to needle penetration. The changes were noted after seven days treatment but were reversed by decreasing the dose concentration.
Table 7 - Chronic Toxicity
| Species | Duration | Max. no-effect Dose (mg/kg/day) | Effects |
|---|---|---|---|
Rat Dog | 18 months 12 months | 1 12 | Usually transient and restricted to highest dose |
Genotoxicity:
No evidence of mutagenicity was observed in microbial mutagen tests using mutant strains of Salmonella typhimurium, Escherichia coli or Saccharomyces cerevisiae, with or without a rat- liver post-mitochondrial metabolizing system.
There was also no evidence of damage to genetic material noted in in vitro V-79 mammalian cell mutation studies, in vitro chromosome aberration tests using human peripheral lymphocytes, or in vivo chromosome aberration assays in mouse bone marrow.
Carcinogenicity:
Table 8 – Carcinogenicity Studies
| Species | Route | Dose (mg/kg/day) | Duration of Study | Results |
|---|---|---|---|---|
Mice Rats | Oral Oral | 1-40 (max. oral dose 30) 1-25 (max. oral dose 10) | 2 years 2 years | No treatment related increases in tumour incidence. Proportion of benign/malignant tumours also remained Consistent with the pathological background of the animals studied. |
There was no evidence of a tumorigenic effect of ondansetron in any tissue.
Reproductive and Developmental Toxicology:
Ondansetron was not teratogenic in rats and rabbits at dosages up to the maximum non- convulsive level, (rat: 15 mg/kg/day, rabbit: 30 mg/kg/day; the maternal dose was approximately 6 and 24 times the maximum recommended human oral dose of 24 mg/day, respectively, based on body surface area). No adverse effects on pregnancy or fetal and post- natal development were detected in rats and no fetal abnormalities were observed in rabbits after oral administration of ondansetron.
A slight maternal toxicity was observed at the highest dose level in intravenous organogenesis (4.0 mg/kg/day) studies in the rabbit. Effects included maternal body weight loss and increased incidence of early fetal death. In a rat fertility study, there was a dose-related decrease in the proportion of surviving pups of the F2 generation; however, the significance of this is unclear.
Administration of ondansetron to pregnant rats and rabbits indicated there was foetal exposure to low levels of ondansetron and its metabolites. Ondansetron is retained in the foetal eye presumably bound to melanin. In rats, the transfer of ondansetron and its metabolites into breast milk was extensive. The concentration of unchanged ondansetron in breast milk was higher than in corresponding plasma samples.
Daily administration of ondansetron at dosages up to 15 mg/kg/day to pregnant rats (a maternal dose of approximately 6 times the maximum recommended human oral dose of 24 mg/day, based on body surface area) from day 17 of pregnancy to litter day 22 had no effects on pregnancy of the parental generation or on post-natal development and mating of the F1 generation. Foetal development of the F2 generation was comparable to controls; however, the number of implantations and viable foetuses was reduced in the highest dosage group when compared with controls.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Pr ONDANSETRON ODT (Orally Disintegrating Tablets, 4 mg and 8 mg, Oral), Submission control 285751, Product Monograph, Sandoz Canada Inc. SEP 25, 2024