


Product Monograph - M-Ambrisentan
Recent Major Label Changes
| 7 Warnings and Precautions, 7.1.3 Pediatrics | 2026-07 |
|---|
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Recent Major Label Changes ......................................................................................................... 2
Table of Contents .......................................................................................................................... 2
Part 1: Healthcare Professional Information .................................................................................. 4
1 Indications ........................................................................................................................ 4
1.1 Pediatrics ...................................................................................................................... 4
1.2 Geriatrics ...................................................................................................................... 4
2 Contraindications .............................................................................................................. 4
4 Dosage and Administration ............................................................................................... 4
4.1 Dosing Considerations .................................................................................................. 4
4.2 Recommended Dose and Dosage Adjustment ............................................................. 5
4.5 Missed Dose .................................................................................................................. 6
5 Overdose .......................................................................................................................... 6
6 Dosage Forms, Strengths, Composition and Packaging ...................................................... 6
7 Warnings and Precautions ................................................................................................ 6
7.1 Special Populations ....................................................................................................... 9
7.1.1 Pregnancy ..................................................................................................................... 9
7.1.2 Breast-feeding ............................................................................................................. 10
7.1.3 Pediatrics .................................................................................................................... 10
7.1.4 Geriatrics .................................................................................................................... 10
8 Adverse Reactions .......................................................................................................... 10
8.1 Adverse Reaction Overview ........................................................................................ 10
8.2 Clinical Trial Adverse Reactions .................................................................................. 11
8.3 Less Common Clinical Trial Adverse Reactions ........................................................... 14
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data ....................................................................................................... 14
8.5 Post-Market Adverse Reactions .................................................................................. 15
9 Drug Interactions ............................................................................................................ 16
9.2 Drug Interactions Overview ........................................................................................ 16
9.4 Drug-Drug Interactions ............................................................................................... 16
9.5 Drug-Food Interactions ............................................................................................... 21
9.6 Drug-Herb Interactions ............................................................................................... 22
9.7 Drug-Laboratory Test Interactions .............................................................................. 22
10 Clinical Pharmacology ..................................................................................................... 22
10.1 Mechanism of Action .................................................................................................. 22
10.2 Pharmacodynamics ..................................................................................................... 22
10.3 Pharmacokinetics .......................................................................................................... 24
11 Storage, Stability and Disposal ........................................................................................ 26
12 Special Handling Instructions .......................................................................................... 26
Part 2 : Scientific Information ...................................................................................................... 27
13 Pharmaceutical Information ........................................................................................... 27
14 Clinical Trials ................................................................................................................... 27
14.1 Clinical Trials by Indication ......................................................................................... 27
14.2 Comparative Bioavailability Studies............................................................................ 38
15 Microbiology ................................................................................................................... 39
16 Non-Clinical Toxicology ................................................................................................... 39
17 Supporting Product Monographs .................................................................................... 41
Patient Medication Information .................................................................................................. 42
Part 1: Healthcare Professional Information
1 Indications
M-AMBRISENTAN (ambrisentan tablets) is indicated for:
- The treatment of idiopathic(‘primary’) pulmonary arterial hypertension (IPAH) and pulmonary arterial hypertension (PAH) associated with connective tissue disease in adult patients with WHO functional class II or III symptoms.
- initiation therapy in combination with tadalafil in adult PAH patients with WHO Functional class II or III symptoms.
M-AMBRISENTAN should only be used by clinicians experienced in the diagnosis and treatment of IPAH or PAH.
1.1 Pediatrics
Pediatrics (< 18 years of age): No clinical data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics and 16 Non-Clinical Toxicology, Juvenile toxicity regarding data available in juvenile animals).
1.2 Geriatrics
Geriatrics (≥ 65 years of age): There is limited safety and effectiveness data in the geriatric population (see 7.1.4 Geriatrics and 10.3 Pharmacokinetics).
2 Contraindications
M-AMBRISENTAN is contraindicated in:
- Patients with a known or suspected hypersensitivity to M-AMBRISENTAN or any of the ingredients in the formulation (see 6 Dosage Forms, Strengths, Composition And Packaging).
- Pregnancy (see 7.1.1 Pregnancy).
- Breastfeeding (see 7.1.2 Breastfeeding).
- Patients with severe hepatic impairment (with or without cirrhosis) (see 7 Warnings And Precautions, Hepatic/Biliary/Pancreatic, and 4 Dosage and Administration).
- Patients with baseline values of hepatic aminotransferases (aspartate aminotransferases (AST) and/or alanine aminotransferases (ALT)) >3 x ULN (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic, and 4 Dosage and Administration).
- Patients with idiopathic pulmonary fibrosis (IPF), with or without pulmonary hypertension.
4 Dosage and Administration
4.1 Dosing Considerations
- Treatment should only be initiated by a physician experienced in the treatment of PAH.
- Assess liver function before starting M-AMBRISENTAN (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic, and Monitoring and Laboratory Tests).
- M-AMBRISENTAN treatment should only be initiated in women of child-bearing potential following a negative pregnancy test and providing they are using a reliable method of contraception (see 2 Contraindications; 7.1.1 Pregnancy).
- M-AMBRISENTAN is contraindicated in patients with severe hepatic impairment and those with baseline AST or ALT >3x ULN. Patients with ALT/AST levels >2 x ULN were not included in a clinical trial studying co-administration of ambrisentan with tadalafil. M-AMBRISENTAN should be used with caution in patients with moderate hepatic impairment (see 7 Warnings and Precautions; 10.3 Pharmacokinetics, and Special Populations and Conditions, Hepatic Insufficiency).
- Patients with PAH associated with connective tissue disease may require 10 mg M-AMBRISENTAN for optimal efficacy. Consider increasing the dose to 10 mg. M-AMBRISENTAN providing the 5 mg dose is well tolerated (see 8 Adverse Reactions).
4.2 Recommended Dose and Dosage Adjustment
Adult Dosage
M-AMBRISENTAN should be initiated at a dose of 5 mg once daily. Additional benefit may be obtained by increasing the dose to 10 mg once daily.
When used in initial combination with tadalafil, the dose of tadalafil should be uptitrated from 20 mg to 40 mg once daily 4 weeks after initiation and M-AMBRISENTAN should be uptitrated from 5 mg to 10 mg after another 4 weeks, if well tolerated (see 14 Clinical Trials).
The maximum recommended daily dose is 10 mg.
When co-administered with cyclosporine A, the dose of M-AMBRISENTAN should be limited to 5 mg once daily (see 9.4 Drug-Drug Interactions, Cyclosporine A).
M-AMBRISENTAN can be administered with or without food.
Pediatrics (< 18 years of age)
No clinical data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics and 16 Non-Clinical Toxicology, Juvenile toxicity regarding data available in juvenile animals). Geriatric patients aged 65 years and over
No dose adjustment is required in patients aged 65 years and over. In clinical monotherapy studies, peripheral edema was reported as dose dependent and more common in patients ≥65 years of age.
Patients with renal impairment
Renal metabolism and excretion of M-AMBRISENTAN is minimal, so dose adjustment is unlikely to be required in patients with renal impairment.
4.5 Missed Dose
If a dose of M-AMBRISENTAN is missed, the patient should be advised to take it as soon as they remember, and then continue with the next dose at the regular interval. Two doses should not be taken at the same time to make up for a missed dose.
5 Overdose
In healthy volunteers, single doses of 50 and 100 mg (5 to 10 times the maximum recommended dose) were associated with headache, flushing, dizziness, nausea, and nasal congestion.
Due to the mechanism of action of ambrisentan tablets, an overdosage of M-AMBRISENTAN could potentially result in hypotension. In the case of pronounced hypotension, active cardiovascular support may be required. No specific antidote is available.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 Dosage Forms, Strengths, Composition and Packaging
Table 1 – Dosage Forms, Strengths, Composition
| Route of Administration | Dosage Form / Composition / Strength | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet, 5 mg and 10 mg | Croscarmellose sodium, FD&C Red #40 aluminum lake, lactose monohydrate, lecithin (soya), magnesium stearate, microcrystalline cellulose, polyethylene glycol /macrogol, polyvinyl alcohol, talc, and titanium dioxide. |
Description
M-AMBRISENTAN 5 mg film-coated tablets are pale pink, square, convex, and debossed with “5” on one side, plain on the other side.
M-AMBRISENTAN 10 mg film-coated tablets are pink, oblong, biconvex, and debossed with “10” on one side, plain on the other side.
M-AMBRISENTAN tablets are available in blister packs of 30 (3 x 10’s) tablets.
7 Warnings and Precautions
Carcinogenesis and Genotoxicity
There are no human data available (see 16 Non-Clinical Toxicology, Carcinogenicity and Genotoxicity).
Driving and Operating Machinery
There have been no studies to investigate the effect of ambrisentan tablets on driving performance or the ability to operate machinery. Further, a detrimental effect on such activities cannot be predicted from the pharmacology of the active substance.
Fluid Retention
Peripheral edema (fluid retention) has been observed with endothelin receptor antagonists (ERAs) including ambrisentan tablets. Peripheral edema may also be a clinical consequence of PAH. Ambrisentan tablets induced a dose-dependent increased incidence of mild to moderate peripheral edema (see 8 Adverse Reactions).
Post-market reports confirm that fluid retention may occur within weeks after starting ambrisentan tablets and, in some cases, has required intervention with a diuretic or hospitalization for fluid management or decompensated heart failure (see 8.2 Clinical Trial Adverse Reactions, Table 2). If patients have pre-existing fluid overload, this should be managed as clinically appropriate prior to starting M-AMBRISENTAN.
If clinically significant peripheral edema develops during therapy with M-AMBRISENTAN, with or without associated weight gain, further evaluation should be undertaken to determine the cause, such as the use of M-AMBRISENTAN or the existence of underlying heart failure. The possible need for specific treatment or discontinuation of M-AMBRISENTAN therapy should also be evaluated.
Fluid retention/peripheral edema is more common during therapy with ambrisentan tablets plus tadalafil than with either ambrisentan tablets or tadalafil alone.
Hematologic
The development of drug-related decreases in hemoglobin concentration and hematocrit has been associated with administration of endothelin receptor antagonists and was observed in clinical studies with ambrisentan tablets in monotherapy. There have been cases where this has resulted in anemia requiring transfusion. These decreases were generally observed within the first few weeks of treatment with ambrisentan tablets, and stabilized thereafter. Anemia is more common during therapy with ambrisentan tablets plus tadalafil than with either ambrisentan tablets or tadalafil alone (see 8 Adverse Reactions).
Initiation of M-AMBRISENTAN is not recommended for patients with clinically significant anemia (see 7 Warnings and Precautions, Monitoring and Laboratory Tests).
Hepatic/Biliary/Pancreatic
Liver function abnormalities have been associated with pulmonary arterial hypertension. Hepatic enzyme elevations potentially related to therapy have been observed with endothelin receptor antagonists (ERAs). Therefore, hepatic function should be evaluated prior to initiation of M-AMBRISENTAN. Monitor liver function as clinically indicated for patients with normal liver function or mild hepatic impairment. Initiation of M-AMBRISENTAN is contraindicated for patients with aminotransferase (alanine aminotransferase, ALT or aspartate aminotransferase, AST) concentrations greater than 3 times the upper limit of normal (>3x ULN) or patients with severe hepatic impairment. Patients with ALT/AST levels >2x ULN were not included in a clinical trial studying co-administration of ambrisentan tablets with tadalafil. M-AMBRISENTAN should be used with caution in patients with moderate hepatic impairment and monthly monitoring of ALT and AST is recommended (see 4 Dosage and Administration, and 10 Clinical Pharmacology).
Although the incidence of aminotransferase abnormalities was low, the possibility of serum aminotransferase elevations associated with ambrisentan tablets administration cannot be excluded. Therefore, monthly monitoring of ALT and AST is recommended in particularly vulnerable patients such as those with moderate hepatic impairment or those with clinically significant right heart failure, pre-existing liver disease, previous elevations of aminotransferases due to medications or taking concurrent medications known to elevate aminotransferases who may be at increased risk for developing elevated aminotransferases on M-AMBRISENTAN. If patients develop clinically significant aminotransferase elevations or if aminotransferase elevations are accompanied by signs or symptoms of hepatic injury (e.g. jaundice), M-AMBRISENTAN therapy should be discontinued.
In patients without clinical symptoms of hepatic injury or of jaundice, re-initiation of M-AMBRISENTAN may be considered following resolution of hepatic enzyme abnormalities. Hepatic injury and autoimmune hepatitis are known to occur in PAH patients and autoantibodies are frequently found in IPAH. Cases consistent with autoimmune hepatitis, including possible exacerbation of underlying autoimmune hepatitis, and hepatic injury have been reported with ambrisentan tablets therapy, although the contribution of ambrisentan tablets to these events is unclear.
Therefore, patients should be monitored for signs of hepatic injury and caution exercised when M-AMBRISENTAN is used alone or concomitantly with other medicinal products known to be associated with hepatic injury as the additive effects of M-AMBRISENTAN with these agents are not known. Management of autoimmune hepatitis in PAH patients should be optimized prior to initiation of M-AMBRISENTAN and during M-AMBRISENTAN therapy. If patients develop signs or symptoms of hepatitis, or suffer exacerbation of existing autoimmune hepatitis, M-AMBRISENTAN should be discontinued.
Other ERAs have been associated with aminotransferase (AST, ALT) elevations, hepatotoxicity, and cases of liver failure (see 8 Adverse Reactions). In patients who develop hepatic impairment after M-AMBRISENTAN initiation, the cause of liver injury should be fully investigated. Discontinue M-AMBRISENTAN if elevations of liver aminotransferases are >3x ULN or if elevations are accompanied by bilirubin >2x ULN, or by signs or symptoms of liver dysfunction and other causes are excluded.
Monitoring and Laboratory Tests
Hemoglobin and Hematocrit
Ambrisentan tablets has been associated with reductions in hemoglobin concentrations and hematocrit. Initiation of M-AMBRISENTAN is not recommended for patients with clinically significant anemia. It is recommended that hemoglobin and/or hematocrit levels are measured prior to the initiation of M-AMBRISENTAN, again at one month, and periodically thereafter as clinically indicated.
Decreases in hemoglobin and/or hematocrit were observed as very common clinical trial adverse drug reactions (see Table 2). In monotherapy studies, the mean decrease in hemoglobin from baseline to the end of treatment for patients receiving ambrisentan tablets in 12-week placebo-controlled studies was 0.8 g/dL Hemoglobin reductions were observed to persist for 4 years. In combination therapy studies, the incidence of anemia was increased when ambrisentan tablets was dosed in combination with tadalafil (15%), compared to the incidence of anemia when ambrisentan or tadalafil were given as monotherapy (7% and 11%, respectively).
If a clinically significant decrease in hemoglobin or hematocrit is observed, and other causes have been excluded, discontinuation of M-AMBRISENTAN should be considered.
Liver Function Tests
Liver transaminase levels should be measured prior to initiation of treatment and subsequently at monthly intervals in vulnerable patients, or generally in any patient as clinically indicated (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
If patients develop clinically significant elevations of transaminases (greater than 3x ULN), or if transaminase elevations are accompanied by signs or symptoms of hepatic injury (such as nausea, vomiting, fever, abdominal pain, jaundice or unusual lethargy or fatigue) or if elevations are accompanied by increases in bilirubin 2xULN, treatment with M-AMBRISENTAN should be stopped.
In patients without clinical symptoms of hepatic injury or jaundice, re-initiation of M-AMBRISENTAN may be considered following resolution of hepatic enzyme abnormalities (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic).
Pulmonary Veno-Occlusive Disease
If patients develop acute pulmonary edema during initiation of M-AMBRISENTAN, the possibility of pulmonary veno-occlusive disease should be considered.
Renal
Ambrisentan tablets has not been studied in individuals with renal impairment. Ambrisentan tablets does not undergo significant renal metabolism or renal clearance (excretion), and therefore dose adjustment is unlikely to be required in patients with renal impairment (see 10.3 Pharmacokinetics).
Reproductive Health
- Fertility
The development of testicular tubular atrophy in male animals has been linked to the chronic administration of ERAs, including ambrisentan (see 16 Non-Clinical Toxicology). The effect on male human fertility is not known (see 14 Clinical Trials and 16 Non-Clinical Toxicology).
Sensitivity/Resistance
M-AMBRISENTAN contains the azo colouring agent FD&C Red #40 Aluminum Lake which may cause allergic-type reactions.
7.1 Special Populations
7.1.1 Pregnancy
The use of M-AMBRISENTAN is contraindicated in pregnant women. Animal studies in rats and rabbits have shown that ambrisentan is teratogenic with reports of increased incidences of fetal malformations and abnormalities following administration of ERAs including ambrisentan (see 16 Non-Clinical Toxicology).
Women of childbearing potential should be advised of the risk of fetal harm if M-AMBRISENTAN is taken during pregnancy. Pregnancy must be excluded before the start of treatment with M-AMBRISENTAN and prevented thereafter by reliable contraception.
Pregnancy tests during treatment with M-AMBRISENTAN are recommended as clinically indicated.
Women of childbearing potential should be advised to contact their physician immediately if they become pregnant or suspect they may be pregnant. If pregnancy is to be continued, M-AMBRISENTAN should be discontinued and alternative treatment should be initiated (see 2 Contraindications and 16 Non-Clinical Toxicology, Reproductive and Developmental Toxicity).
7.1.2 Breast-feeding
It is unknown if ambrisentan is excreted in human milk. Therefore, breastfeeding is contraindicated in patients taking M-AMBRISENTAN (see 2 Contraindications).
7.1.3 Pediatrics
Pediatrics (< 18 years of age): No clinical data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 16 Non-Clinical Toxicology).
In addition, animal studies indicated a risk of a decrease in brain weight (compared to controls); the clinical relevance of this finding is unknown but may be considered a higher potential risk for children under 4 years of age (see 16 Non-Clinical Toxicology, Juvenile toxicity).
7.1.4 Geriatrics
Geriatrics (>65 years of age): No dose adjustment is required in patients aged 65 years and over. In clinical studies where ambrisentan tablets was used in monotherapy, peripheral edema was reported as dose dependent, was more common and tended to be more severe in patients ≥65 years of age. In a subsequent clinical study (AMBITION), incidence of edema for patients on ambrisentan monotherapy was 19% in patients <55 years, and 28% for those ≥55 years of age (see 8 Adverse Reactions, 10 Clinical Pharmacology, Special Populations and Conditions and 4 Dosage And Administration).
8 Adverse Reactions
8.1 Adverse Reaction Overview
The safety of ambrisentan tablets has been evaluated in Phase II and Phase III clinical studies totalling 483 patients with PAH who were treated with doses of 1, 2.5, 5, or 10 mg once daily, ranging in exposure from 1 day to 3.5 years. Overall, ambrisentan tablets was well tolerated.
In placebo-controlled 12-week studies, the most commonly (≥10%) reported adverse drug reactions with ambrisentan tablets were peripheral edema, headache, and nasal congestion (see Table 2).
In placebo-controlled phase III studies, the proportion of subjects who discontinued because of adverse events was similar across all treatment groups: 3.0% in the placebo group and 2.3% in the ambrisentan tablets group.
In the placebo-controlled studies, six (4.5%) subjects in the placebo group died and 4 (1.5%) subjects in the ambrisentan tablets groups died. A higher proportion of subjects in the placebo group had at least one non-fatal serious adverse event (SAE) compared to the ambrisentan tablets -treated patients. The most frequent SAEs for both the placebo and ambrisentan tablets -treated patients were right ventricular failure (placebo, 6.1%; ambrisentan tablets, 1.1%) and (worsening) pulmonary hypertension (placebo, 3.8 %; ambrisentan tablets, 1.1 %). Treatment-related SAEs occurred with a similar frequency across all ambrisentan tablets treatment groups.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. Therefore, the frequencies of adverse reactions observed in the clinical trials may not reflect frequencies observed in clinical practice and should not be compared to frequencies reported in clinical trials of another drug.
Experience from Short-term Clinical Studies
The following safety data for ambrisentan tablets were obtained from two Phase III 12-week placebo-controlled studies in subjects with PAH (ARIES-1 and ARIES-2). A total of 197 patients received ambrisentan tablets at doses of 5 or 10 mg once daily and 132 patients received placebo.
The adverse drug reactions observed in ARIES-1 and ARIES-2 are summarized in Table 2.
Table 2 Adverse Drug Reactions for PAH Patients Receiving Ambrisentan Tablets in Short-Term Studies (ARIES-1 and ARIES-2, integrated analysis)
| System Organ Class/preferred Term | Placebo (n = 132) (%) | Ambrisentan Tablets 5 mg (n = 130) (%) | Ambrisentan Tablets 10 mg (n = 67) (%) | ||||||
|---|---|---|---|---|---|---|---|---|---|
| Blood and lymphatic system disorders | |||||||||
| Anemia | 2 (1.5) | 2 (1.5) | 2 (3.0) | ||||||
| Cardiac disorders | |||||||||
| Palpitations | 3 (2.3) | 5 (3.8) | 3 (4.5) | ||||||
| Gastrointestinal disorders | |||||||||
| Constipation | 2 (1.5) | 4 (3.1) | 4 (6.0) | ||||||
| Abdominal paina | 1 (0.8) | 6 (4.6) | 4 (6.0) | ||||||
| General disorders and administration site conditions | |||||||||
| Peripheral edema | 14 (10.6) | 24 (18.5) | 19 (28.4) | ||||||
| Fluid retentionb | 4 (3.0) | 4 (3.1) | 4 (6.0) | ||||||
| Nervous system disorders | |||||||||
| Headache | 18 (13.6) | 20 (15.4) | 13 (19.4) | ||||||
| Respiratory, thoracic and mediastinal disorders | |||||||||
| Nasal congestion | 2 (1.5) | 7 (5.4) | 7 (10.4) | ||||||
| Nasopharyngitis | 1 (0.8) | 7 (5.4) | 2 (3.0) | ||||||
| Sinusitis | 0 | 4 (3.1) | 3 (4.5) | ||||||
| Vascular disorders | |||||||||
| Flushingc | 2 (1.5) | 5 (3.8) | 1 (1.5) | ||||||
- a) Includes Abdominal Pain Upper b) Includes Fluid Retention, Fluid Overload, and Local Swelling
- c) Includes Hot Flush.
Adverse drug reactions in short-term monotherapy trials were generally mild to moderate. The higher dose (10 mg) was associated with a higher incidence of peripheral edema, headache, nasal congestion, palpitations, constipation sinusitis, anemia, abdominal pain, and fluid retention. Peripheral edema was the most common adverse drug reaction observed with ambrisentan tablets, and incidence rates varied with age. Among younger patients (<65 years), the incidence was 18% (28/155) among those receiving ambrisentan tablets compared to 13% (13/104) receiving placebo. Among elderly patients (≥65 years), the incidence of peripheral edema was greater: 36% (15/42) among those receiving ambrisentan tablets compared to 4% (1/28) receiving placebo. The results of such subgroup analyses must be interpreted cautiously.
Experience from Long-term Clinical Studies
The long-term safety (>3 months) of ambrisentan tablets in monotherapy was evaluated in 383 patients with PAH in the ARIES-E study, a non-placebo controlled clinical trial extension of ARIES-1 and ARIES-2. The long-term safety of ambrisentan tablets used in combination with tadalafil was evaluated in 302 patients with PAH in a double-blind, active-controlled clinical trial (>3 months; median exposure 534 days), AMBITION. The adverse drug reactions observed were generally consistent with the safety profile of ambrisentan tablets used alone. Adverse drug reactions observed in long-term studies ARIES-E and AMBITION are summarized in Table 3.
Table 3 Adverse Drug Reactions for PAH Patients Receiving Ambrisentan Tablets in Long-term Studies (>3 months), AMBITION and ARIES-E data
| System Organ Class/preferred Term | ARIES-E Ambrisentan Monotherapy n = 383 (%) | AMBITION Combination Therapy (ITT) n = 302 (%) | AMBITION Ambrisentan Monotherapy (ITT) n = 152 (%) | AMBITION Tadalafil Monotherapy (ITT) n=151 (%) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| System Organ Class/preferred Term | ARIES-E Ambrisentan Monotherapy n = 383 (%) | AMBITION Combination Therapy (ITT) n = 302 (%) | AMBITION Ambrisentan Monotherapy (ITT) n = 152 (%) | AMBITION Tadalafil Monotherapy (ITT) n=151 (%) | ||||||||
| Blood and lymphatic system disorders | ||||||||||||
| Anemia | 52 (14) | 44 (15) | 11 (7) | 17 (11) | ||||||||
| Cardiac disorders | ||||||||||||
| Palpitations | 50 (13) | 33 (11) | 23 (15) | 20 (13) | ||||||||
| Eye disorders | ||||||||||||
| Visual impairmenta | 13 (3) | 22 (7) | 8 (5) | 7 (5) | ||||||||
| Gastrointestinal disorders | ||||||||||||
| Nausea | 53 (14) | 45 (15) | 23 (15) | 23 (15) | ||||||||
| Vomiting | 30 (8) | 35 (12) | 13 (9) | 13 (9) | ||||||||
| Constipation | 33 (9) | 16 (5) | 10 (7) | 6 (4) | ||||||||
| Abdominal painb | 55 (14) | 17 (6) | 14 (9) | 15 (10) | ||||||||
| General disorders and administration site conditions | ||||||||||||
| Peripheral edema | 168 (44) | 135 (45) | 58 (38) | 43 (28) | ||||||||
| Fluid retentionc | 24 (6) | 34 (11) | 16 (11) | 18 (12) | ||||||||
| Fatigue | 47 (12) | 34 (11) | 22 (14) | 20 (13) | ||||||||
| Asthenia | 20 (5) | 8 (3) | 4 (3) | 9 (6) | ||||||||
| Immune system disorders | ||||||||||||
| Hypersensitivityd | 13 (3) | 5 (2) | 1 (<1) | 2 (1) | ||||||||
| Nervous system disorders | ||||||||||||
| Headache | 96 (25) | 125 (41) | 51 (34) | 53 (35) | ||||||||
| Dizziness | 66 (17) | 56 (19) | 30 (20) | 22 (15) | ||||||||
| Respiratory, thoracic and mediastinal disorders | ||||||||||||
| Nasal congestion | 48 (13) | 58 (19) | 25 (16) | 17 (11) | ||||||||
| Nasopharyngitis | 58 (15) | 51 (17) | 31 (20) | 23 (15) | ||||||||
| Sinusitis | 39 (10) | 22 (7) | 10 (7) | 11 (7) | ||||||||
| Dyspnoeae | 64 (17) | 55 (18) | 31 (20) | 31 (21) | ||||||||
| Skin and subcutaneous tissue disorders | ||||||||||||
| Rashf | 27 (7) | 28 (9) | 8 (5) | 9 (6) | ||||||||
| Vascular disorders | ||||||||||||
| Flushingg | 23 (6) | 46 (15) | 22 (14) | 16 (11) | ||||||||
- a) Visual impairment includes Vision blurred and Visual disturbance. b) Abdominal pain includes Abdominal pain upper c) Fluid retention includes Fluid retention, Fluid overload, and Local swelling d) Hypersensitivity includes Drug hypersensitivity e) Dyspnea includes Dyspnea exertional. f) Rash includes Rash erythematous, Rash generalised, Rash macular, Rash papular, and Rash pruritic g) Flushing includes Hot flush.
In general, no new or unexpected adverse events were observed during the long-term extension of ARIES-1 and ARIES-2 which had lasted 12 weeks. Of the 67 (18%) deaths during the extension study, six serious adverse reactions observed in four patients (N=32; 13%) were considered by the investigators to be causally related to ambrisentan tablets.
An adverse event led to permanent discontinuation of 85 (22%) patients due mainly to worsening of pulmonary hypertension (5.2%) and right ventricular failure. Sixteen (4%) subjects had ALT and/or AST elevation >3 times the upper limit of normal which led to discontinuation of only one patient. Decrease in hemoglobin persisted for the full duration of treatment. Patients on warfarin or other anticoagulants had no clinically relevant changes in mean PT or INR.
Experience from a Clinical Study with Ambrisentan Tablets Used in Combination with Tadalafil
As described above in Experience from Long Term Clinical Studies, the long-term safety of ambrisentan used in combination with tadalafil was evaluated in a double-blind, active-controlled clinical trial, AMBITION. The adverse drug reactions observed were generally consistent with the safety profile of ambrisentan used alone (see Table 3). Table 4 below presents the adverse reactions seen more frequently in the combination of ambrisentan tablets with tadalafil than with either drug alone.
Table 4 Adverse Drug Reactions for PAH Patients Receiving Ambrisentan Tablets in AMBITION Long-term Study (>3 months) with ≥2% Higher Incidence in the Combination Therapy Arm versus either of the Monotherapy Arms by Decreasing Incidence in Combination Arm
| Preferred Term | AMBITION Combination Therapy (ITT) n=302 (%) | AMBITION Ambrisentan Monotherapy (ITT) n=152 (%) | AMBITION Tadalafil Monotherapy (ITT) n=151 (%) |
|---|---|---|---|
| Peripheral edema | 135 (45) | 58 (38) | 43 (28) |
| Headache | 125 (41) | 51 (34) | 53 (35) |
| Nasal congestion | 58 (19) | 25 (16) | 17 (11) |
| Dizziness | 56 (19) | 30 (20) | 22 (15) |
| Flushinga | 46 (15) | 22 (14) | 16 (11) |
| Anemia | 44 (15) | 11 (7) | 17 (11) |
| Vomiting | 35 (12) | 13 (9) | 13 (9) |
| Rashb | 28 (9) | 8 (5) | 9 (6) |
| Visual impairmentc | 22 (7) | 8 (5) | 7 (5) |
| Tinnitus | 8 (3) | 1 (<1) | 0 (0) |
- a)
Flushing includes Hot flush. b) Rash includes Rash erythematous, Rash generalised, Rash macular, Rash papular, and Rash pruritic. c) Visual impairment includes Vision blurred.
In the AMBITION study, the incidence of peripheral edema in elderly patients (≥65 years) was 44% (44/101), 37% (18/49) and 29% (16/56) in the ambrisentan tablets + tadalafil, ambrisentan tablets monotherapy and tadalafil monotherapy groups respectively, compared to 45% (91/201), 39% (40/103) and 28% (27/95) in younger patients (<65 years).
8.3 Less Common Clinical Trial Adverse Reactions
The following less common clinical trial adverse reaction occurred in PAH patients receiving ambrisentan tablets in phase III 12-week placebo-controlled studies in subjects with PAH (ARIES-1 and ARIES-2):
Immune system disorders: Hypersensitivity
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Hematologic Changes
In the placebo-controlled Phase III studies in patients with PAH, the mean changes from baseline (in patients receiving placebo, ambrisentan tablets 5 mg and 10 mg, respectively) were (+0.15, -0.77, -0.93) for hemoglobin and (+0.01%, -2%, -3%) for hematocrit.These changes were not dose-related in patients receiving ambrisentan tablets 5 mg and 10 mg. Marked decreases in hemoglobin (> 15% decrease from baseline resulting in a value below the lower limit of normal) were observed in 7% of patients receiving ambrisentan tablets and 4% of patients receiving placebo. Similar decreases in hemoglobin/hematocrit have been observed with other ERAs; the cause of the decrease is not fully understood, but it is not due to hemorrhage or hemolysis. The incidence of anemia was increased when ambrisentan tablets was dosed in combination with tadalafil (15% adverse event frequency), compared to the incidence of anemia when ambrisentan or tadalafil were given as monotherapy (7% and 11%, respectively). Adverse events related to anemia, low hemoglobin or low hematocrit appeared to be more frequent with 10 mg ambrisentan tablets than lower doses or placebo. Mean decreases from baseline (ranging from 0.9 to 1.2 g/dL) in hemoglobin concentrations persisted for up to 4 years of treatment with ambrisentan tablets in the long-term open-label extension of the pivotal Phase III clinical studies.
Clinical Chemistry Change
A number of patients (19%) showed an increase of γGT (>3x ULN). The clinical significance is not known.
8.5 Post-Market Adverse Reactions
In addition to adverse drug reactions identified from clinical studies, the following adverse drug reactions were identified during post-approval use of ambrisentan tablets. Events of ‘unknown’ frequency have been reported voluntarily from a population of unknown size, therefore estimates of frequency cannot be made.
Cardiac Disorders
Fluid retention and heart failure associated with fluid retention occurring within weeks after starting ambrisentan tablets therapy have been reported post-marketing. In some cases, these events have required intervention with a diuretic or hospitalization for fluid management or decompensated heart failure.
Blood and Lymphatic System Disorders
Anemia requiring transfusion.
Hepatobiliary Disorders
Cases of increased hepatic transaminases (AST and ALT >3x ULN), autoimmune hepatitis (see 7 Warnings and Precautions), including cases of exacerbation of autoimmune hepatitis, and hepatic injury of unclear etiology (including increased blood bilirubin >2x ULN) have been reported during ambrisentan tablets therapy. In the AMBITION study, in a subset of patients without left ventricular dysfunction, the incidence of liver adverse events (primarily increased levels of liver enzymes) occurred in 7% of patients of the ambrisentan tablets plus tadalafil combination therapy group, versus in 2% and 5% of patients in the ambrisentan tablets monotherapy and tadalafil monotherapy groups, respectively. The incidence of liver events was similar in patients with left ventricular dysfunction.
Vascular Disorders
Hypotension: In the AMBITION study, in a subset of patients without left ventricular dysfunction, the rates of adverse events potentially indicative of hypotension (hypotension, dizziness, syncope, presyncope, vasodilatation, blood pressure decreased, orthostatic hypotension, dizziness exertional, dizziness postural, hypovolemic shock) and the rates of the adverse event of hypotension itself were: 32% and 8% in the ambrisentan tablets + tadalafil arm, compared to 27% and 7% in the ambrisentan, and 27% and 7% in the tadalafil monotherapy arms. Including patients with left ventricular dysfunction, the rates of adverse events potentially indicative of hypotension and hypotension itself were: 30% and 8% in the ambrisentan tablets + tadalafil arm, compared to 29% and 7% in the ambrisentan, and 30% and 8% in the tadalafil monotherapy arms.
9 Drug Interactions
9.2 Drug Interactions Overview
Studies with human liver tissue indicate that ambrisentan is metabolized by uridine 5’-diphosphate glucuronosyltransferases (UGTs) 1A9S, 2B7S, and 1A3S, CYP3A4 and CYP2C19. In vitro studies suggest that ambrisentan is a substrate of Organic Anion Transport Protein (OATP). In vitro studies also show ambrisentan is a substrate but not an inhibitor of P-glycoprotein (P-gp).
In vitro data show that ambrisentan at concentrations up to 300mcM does not markedly inhibit UGT1A1, UGT1A6, UGT1A9, UGT2B7 or cytochrome P450 enzymes 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1 and 3A4. Further, in vitro studies using cell-lines transfected with the human transporter genes showed that ambrisentan does not inhibit P-gp, breast cancer receptor protein (BCRP), multi-drug resistance related protein 2 (MRP2), or bile salt export pump (BSEP) at concentrations up to 100mcM. Ambrisentan showed weak in vitro inhibition of OATP1B1, OATP1B3 and sodium-taurocholate co-transporter (NTCP) with IC50 values of 47mcM, 45mcM, and approximately 100mcM, respectively. In vitro studies in rat and human hepatocytes showed no evidence for ambrisentan inhibition of NTCP, OATP, BSEP and MRP2. Furthermore, ambrisentan did not induce MRP2, P-gp or BSEP protein expression in rat hepatocytes. Taken together, the in vitro data suggest that ambrisentan, at clinically relevant concentrations, would not be expected to have an effect on UGT1A1, UGT1A6, UGT1A9, UGT2B7 or cytochrome P450 enzymes 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1, 3A4 or transport via BSEP, BCRP, P-gp, MRP2, OATP1B1/3, or NTCP.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction.
Table 5 - Established or Potential Drug-Drug Interactions
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
|---|---|---|---|---|
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
| Non-proprietary name(s) of the drug product(s) | Source of evidence | Effect | Clinical comment | |
| Cyclosporine A | CT | The effects of repeat dosing of cyclosporine A (100 – 150 mg twice daily) on the steady-state pharmacokinetics of ambrisentan tablets (5 mg once daily), and the effects of repeat dosing of ambrisentan tablets (5 mg once daily) on the steady-state pharmacokinetics of cyclosporine A (100 – 150 mg twice daily) were studied in healthy volunteers. The Cmax and AUC(0–τ) of ambrisentan tablets increased (48% and 121%, respectively) in the presence of multiple doses of cyclosporine A. The apparent plasma t1/2 of ambrisentan tablets in the presence of cyclosporine increased by 38% as | The dose of M-AMBRISENTAN should be limited to 5 mg once daily when co-administered with cyclosporine A (see 4.2 Recommended Dose and Dosage Adjustment). No dose adjustment of cyclosporine A is warranted. | |
| compared to ambrisentan tablets alone (from 8.36h to 11.5h). No important differences in the median tmax were observed. However, multiple doses of ambrisentan tablets had no clinically relevant effect on cyclosporine A exposure. It should be noted that the apparent mean t1/2 value of cyclosporine A increased by 32% from 4.79h (cyclosporine A alone) to 6.33h in the presence of ambrisentan tablets. | ||||
Phosphodiesterase inhibitors (Sildenafil; Tadalafil) | CT | In healthy volunteers, co-administration of ambrisentan tablets with a phosphodiesterase inhibitor, (either sildenafil or tadalafil) did not significantly affect the pharmacokinetics of the phosphodiesterase inhibitor or ambrisentan tablets. The effects of steady-state ambrisentan tablets (10 mg once daily) on the pharmacokinetics of a single dose of tadalafil, and the effects of steady-state tadalafil (40 mg once daily) on the pharmacokinetics of a single dose of ambrisentan tablets were studied in 23 healthy volunteers. Ambrisentan tablets did not have any clinically relevant effects on the pharmacokinetics of tadalafil. Similarly, co-administration with tadalafil did not affect the pharmacokinetics of ambrisentan tablets. In healthy volunteers receiving a single dose of sildenafil (20 mg), daily doses of ambrisentan tablets (10 mg) did not have a clinically relevant effect on the | The co-administration of ambrisentan tablets with tadalafil was studied in a multicenter, double-blind, active-controlled study. See 7 Warnings and Precautions, 8 Adverse Reactions, 4 Dosage and Administration, And 14 Clinical Trials | |
pharmacokinetics of sildenafil or the active metabolite, n-desmethyl sildenafil. Similarly, daily doses of sildenafil (20 mg tid) did not have a clinically relevant effect on the pharmacokinetics of a single dose of ambrisentan tablets (10 mg) (see, 10.3 Pharmacokinetics). | ||||
| Ketoconazole | CT | Steady-state administration of ketoconazole increased the AUC∞ and Cmax of ambrisentan tablets by 35% and 20%, respectively. The clinical significance of these changes is not known. | Patients on 10 mg of M-AMBRISENTAN while on ketoconazole should be monitored closely for any signs of adverse effects. | |
| Digoxin | CT | The effects of repeat dosing of ambrisentan tablets (10 mg) on the pharmacokinetics of single dose digoxin were studied in 15 healthy volunteers. Multiple doses of ambrisentan tablets resulted in slight but significant increases in digoxin AUC(0-last) (16%) and trough concentrations, and a 29% increase in digoxin Cmax. The increase in digoxin exposure (by 9% of AUC(0-∞)) observed in the presence of multiple doses of ambrisentan tablets was not considered clinically relevant | No dose adjustment of digoxin is warranted. However, given the narrow therapeutic index of digoxin, caution and monitoring are recommended. | |
| Oral contraceptives | CT | In a clinical study in healthy volunteers, steady-state dosing with ambrisentan tablets 10 mg once daily did not significantly affect the single-dose pharmacokinetics of the ethinyl estradiol and norethindrone components of a combined oral contraceptive. Based on this pharmacokinetic study, ambrisentan tablets would not be expected to significantly affect exposure to oestrogen- or progestogen-based contraceptives. The effects of 12 days dosing with ambrisentan tablets (10 mg once daily) on the pharmacokinetics of a single dose of oral contraceptive containing ethinyl estradiol (35 mcg) and norethindrone (1 mg) were studied in healthy female volunteers. The Cmax and AUC(0–∞) were slightly decreased for ethinyl estradiol (8% and 4%, respectively), and slightly increased for norethindrone (13% and 14 %, respectively). These changes in exposure to ethinyl estradiol or | No dose adjustment is warranted. | |
| norethindrone were small and are unlikely to be clinically significant. | ||||
| Strong 2C19 inhibitor (omeprazole) | CT | In clinical studies of patients with PAH, co-administration of ambrisentan tablets and omeprazole (an inhibitor of CYP2C19) did not significantly affect the pharmacokinetics of ambrisentan tablets. | No dose adjustment is warranted. | |
| Rifampin | CT | The effects of acute and repeat dosing of rifampin (600 mg once daily) on the steady-state pharmacokinetics of ambrisentan tablets (10 mg once daily) were studied in healthy volunteers. Following initial doses of rifampin, a transient increase in ambrisentan tablets AUC(0–τ) (121% and 116% after first and second doses of rifampin, respectively) was observed. Apparent plasma t1/2 of ambrisentan tablets decreased by 50% from 8.28h to 4.59h when co-administered with rifampin. However, there was no clinically relevant effect on ambrisentan tablets exposure by day 8, following administration of multiple doses of rifampin. | No dose adjustment of M-AMBRISENTAN is warranted upon concomitant administration with rifampin. | |
| Warfarin | CT | In healthy volunteers receiving warfarin, daily doses of ambrisentan tablets (10 mg) did not have a clinically relevant effect on prothrombin time (PT), International Normalized Ratio (INR), or the pharmacokinetics of S-warfarin (CYP2C9 substrate) or R-warfarin (CYP3A4 substrate). In patients with PAH receiving warfarin-type anticoagulants, concomitant administration of ambrisentan tablets did not result in a clinically relevant change in PT, INR or anticoagulant dose (see 10.3 Pharmacokinetics). | No dose adjustment is warranted. | |
CT = Clinical Trial
9.5 Drug-Food Interactions
M-AMBRISENTAN can be taken with or without food (see 10.3 Pharmacokinetics).
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 Clinical Pharmacology
10.1 Mechanism of Action
Ambrisentan is an orally active, propanoic acid-class, endothelin receptor antagonist (ERA) that is selective for the endothelin type A (ETA) receptor. Selective inhibition of the ETA receptor inhibits phospholipase C-mediated vasoconstriction and protein kinase C-mediated cell proliferation, while preserving nitric oxide and prostacyclin production, cyclic GMP- and cyclic AMP-mediated vasodilation, and endothelin-1 (ET-1) clearance that is associated with the endothelin type B (ETB) receptor.
Ambrisentan is a specific, competitive endothelin receptor antagonist, with ETA receptor selectivity. This pharmacologic property is the primary mode of action of ambrisentan.
Pharmacological activity of ambrisentan has been evaluated in a series of assays and animal models.
10.2 Pharmacodynamics
Cardiopulmonary Hemodynamics
Invasive hemodynamic parameters were assessed in patients with pulmonary arterial hypertension (PAH) at baseline and after 12 weeks (n=29) in a Phase II study. The cardiac index for treatment with ambrisentan tablets 5 mg and 10 mg was increased by 0.5 L/min/m2 (95% CI: -0.01 to 0.95; p=0.0518) and 0.4 L/min/m2 (95% CI: -0.02 to 0.76; p=0.0560), respectively. The mean pulmonary artery pressure for treatment with ambrisentan tablets 5 mg and 10 mg were -4.3 mmHg (95% CI: -8.0 to -0.6; p=0.0272) and -13.3 mmHg (95% CI: -26.1 to -0.6; p=0.0460), respectively. The mean pulmonary vascular resistance for treatment with ambrisentan tablets 5 mg and 10 mg were -3.5 mmHg/L/min (95% CI: -6.0 to -0.94; p=0.0131) and -4.3 mmHg/L/min (95% CI: -11.3 to 2.7; p=0.1179), respectively. There was no significant reduction in mean right atrial pressure.
B-type Natriuretic Peptide
Two Phase III placebo-controlled studies demonstrated that plasma concentrations of BNP in patients who received ambrisentan tablets for 12 weeks decreased by 29% in the 2.5 mg, 30% in the 5 mg, and 45% in the 10 mg group (p < 0.001 for each dose group) and increased by 11% in the placebo group.
In patients with PAH who received combination therapy with ambrisentan tablets and tadalafil in the AMBITION study, greater decreases from baseline in N-terminal pro-B-type natriuretic peptide (NT-pro-BNP) were observed relative to ambrisentan tablets monotherapy (geometric least-squares mean percent decreases of 67% versus 56%, respectively; p = 0.0111) or versus tadalafil monotherapy (44% decrease; p < 0.0001).
The decrease in NT-pro-BNP was observed early (Week 4) and was sustained through Week 24.
Cardiac Electrophysiology
In a randomized, positive- and placebo-controlled, parallel-group study, healthy subjects received either ambrisentan tablets 10 mg daily followed by a single dose of 40 mg, placebo followed by a single dose of moxifloxacin 400 mg, or placebo alone. Ambrisentan tablets 10 mg daily had no significant effect on the QTc interval. The 40 mg dose of ambrisentan tablets increased mean QTc at tmax by 5 ms with an upper 95% confidence limit of 9 ms. The effect of concomitant therapy of ambrisentan tablets with metabolic inhibitors of ambrisentan (i.e. ketoconazole, cyclosporine A) on QT prolongation is unknown (see 9 Drug Interactions).
Primary Pharmacodynamics
In vitro studies using membrane preparations from human ventricular myocytes, showed that ambrisentan is an endothelin antagonist with a Ki of 16 pM against ETA receptors. The selectivity of ambrisentan for ETA receptors over ETB receptors is about 4000-fold. The relative affinity of the R-enantiomer was markedly weaker as compared to the value for the S-enantiomer.
In vivo studies have been performed in a rat model of endothelin-induced hypertension. Ambrisentan dose-dependently (1, 3, or 10 mg/kg p.o.) reduced the increases in arterial pressure resulting from endothelin (Big ET-1) infusion.
No studies were performed on the pharmacodynamic effects of ambrisentan in animal models of pulmonary hypertension.
Secondary Pharmacodynamics
When tested for specificity using a battery (100) of receptors and ion channels, ambrisentan at 10 mcM was not active (< 50% inhibition). The R-enantiomer and 4-hydroxymethyl metabolite of ambrisentan were also inactive in a similar specificity panel.
In normotensive rats, oral administration of 300 mg/kg of ambrisentan or intravenous administration of 100 mg/kg ambrisentan caused initial increases in arterial pressure and heart rate that were followed by sustained reductions in these cardiovascular parameters.
In normotensive dogs, oral administration of 1, 10, and 100 mg/kg of ambrisentan caused dose-dependent reductions in arterial pressure that were not compensated for by increased heart rate.
Safety Pharmacology
Safety pharmacology studies were conducted to examine the effect of ambrisentan on the central and peripheral nervous system, cardiovascular and respiratory, gastrointestinal and renal systems, as well as cardiac conductivity (hERG cell current and guinea pig papillary muscle), uterine smooth muscle contractility, blood coagulation and spleen cell mitogenicity.
There was no evidence of overt central or peripheral effects in mice and rats after intravenous and oral administration of doses up to 100 mg/kg and 300 mg/kg, respectively.
The results from these safety pharmacology tests indicate that high concentrations of ambrisentan produced little to no effects in in vitro, ex vivo and in whole animal models and suggests minimal risk for off-target biological effects; however, large single doses of ambrisentan could lower arterial pressure and have the potential for causing hypotension and symptoms related to vasodilation. In addition, in rats, ambrisentan (single i.v. or oral doses) reduced renal sodium, chloride and calcium excretion rates in a dose-dependent manner.
No pharmacodynamic drug interaction studies were performed.
Long-term Treatment
Eligible Patients from the two pivotal studies, ARIES-1 and ARIES-2, were enrolled into an open-label extension study: ARIES-E. The main purpose of ARIES-E was to evaluate the incidence and severity of adverse events associated with long-term exposure to ambrisentan
tablets, including the effects on serum amino transferases. Patients who received ambrisentan tablets in ARIES-1 and ARIES-2 remained on their current dose at enrolment into ARIES-E, whereas patients who received placebo were randomized to ambrisentan tablets 2.5 mg, 5 mg or 10 mg once daily (N=383). Patients could be up-titrated or down-titrated and could receive prostanoid drugs approved for PAH therapy as needed in the course of ARIES-E (13% of patients required prostanoid therapy). Of the 96 patients on 2.5 mg, 190 on 5 mg and 97 on 10 mg at randomization, 82%, 68% and 49% remained in the study at 1, 2 and 3 years, respectively and 91%, 83%, 79% of these patients were on ambrisentan tablets monotherapy during these time periods.
Survival
In ARIES-E, patients who were treated with ambrisentan tablets (2.5 mg, 5 mg, or 10 mg once daily), Kaplan-Meier estimates of survival at 1, 2, and 3 years were 93%, 85%, and 79%, respectively. Of the patients who remained on ambrisentan tablets for up to 3 years, the majority received no other treatment for PAH as mentioned above. A dose-response relationship was not observed. These uncontrolled observations do not allow comparison with a group not given ambrisentan tablets and cannot be used to determine the long-term effect of ambrisentan tablets on mortality.
Efficacy
In general, benefits observed during the placebo-controlled trials, ARIES-1 and ARIES-2, were maintained in the majority of the patients remaining in ARIES-E during the full period of observation.
10.3 Pharmacokinetics
Absorption
Ambrisentan is absorbed rapidly in humans. The absolute bioavailability of ambrisentan is not known. After oral administration, maximum plasma concentrations (Cmax) of ambrisentan typically occurs between 1 and 2 hours post dose under both fasted and fed conditions. Cmax and area under the plasma concentration-time curve (AUC) increase dose proportionally over the therapeutic dose range. Steady-state is generally achieved following 4 days of repeat dosing.
A food-effect study involving administration of ambrisentan tablets to healthy volunteers under fasting conditions and with a high-fat meal indicated that the Cmax was decreased 12% while the AUC remained unchanged. This decrease in peak concentration is not clinically significant, and therefore M-AMBRISENTAN can be taken with or without food.
Distribution
Ambrisentan is highly plasma protein bound. The in vitro plasma protein binding of ambrisentan was, on average, 99% and independent of concentration over the range of 0.2 - 20 mcg/mL. Ambrisentan is primarily bound to albumin (96.5%) and to a lesser extent to alpha1-acid glycoprotein.
The distribution of ambrisentan into red blood cells is low, with a mean blood: plasma ratio of 0.57 and 0.61 in males and females, respectively.
Metabolism
Ambrisentan is primarily glucuronidated via several UGT isoenzymes (UGT1A9S, UGT2B7S, and UGT1A3S) to form ambrisentan glucuronide (13%). To a lesser extent, ambrisentan also undergoes oxidative metabolism mainly by CYP3A4 and to an even lesser extent by CYP3A5 and CYP2C19 to form 4-hydroxymethyl ambrisentan (21%) which is further glucuronidated to 4-hydroxymethyl ambrisentan glucuronide (5%). The binding affinity of 4-hydroxymethyl ambrisentan for the human endothelin receptor is 65-fold less than ambrisentan. Therefore at concentrations observed in the plasma (approximately 20% relative to parent ambrisentan), 4-hydroxymethyl ambrisentan is not expected to contribute to pharmacological activity of ambrisentan.
Interaction of ambrisentan with UGTs, cytochromes and drug transporters have been studied in vitro (see 9.4 Drug-Drug Interactions).
Elimination
Ambrisentan and its metabolites are primarily found in the feces following hepatic and/or extra-hepatic metabolism. Approximately 22% of the administered dose is recovered in the urine following oral administration with 3.3% being unchanged ambrisentan. The half-life after multiple dosing is approximately 15 hours (range 13.6 to 16.5 hours) in healthy volunteers and 9 to 15 hours in PAH patients. The mean oral clearance of ambrisentan is 38 mL/min and 19 mL/min in healthy subjects and in PAH patients, respectively.
Special Populations and Conditions
Pediatrics
Pediatrics (< 18 years of age): No clinical data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use (see 7.1.3 Pediatrics and 16 Non-Clinical Toxicology, Juvenile toxicity regarding data available in juvenile animals). Geriatrics
Based on the results of a population pharmacokinetic analysis in healthy volunteers and patients with PAH, the pharmacokinetics of ambrisentan tablets were not significantly influenced by age (see 4 Dosage and Administration).
Gender
Based on the results of a population pharmacokinetic analysis in healthy volunteers and patients with PAH, the pharmacokinetics of ambrisentan tablets were not significantly influenced by gender.
Hepatic Insufficiency
The pharmacokinetics of ambrisentan tablets in patients with severe hepatic impairment or with clinically significant elevated hepatic transaminases has not been studied. However, since the main routes of metabolism of ambrisentan are glucuronidation and oxidation with subsequent elimination in the bile, hepatic impairment might be expected to increase exposure (Cmax and AUC) of ambrisentan, however the magnitude of this and any effect on safety and efficacy has not been evaluated. Therefore, M-AMBRISENTAN is contraindicated in patients with severe hepatic impairment or levels of ALT/AST >3x ULN. Patients with ALT/AST levels >2 x ULN were not included in a clinical trial studying co-administration of ambrisentan tablets with tadalafil. M-AMBRISENTAN should be used with caution in patients with moderate hepatic impairment (see 7 Warnings and Precautions, Hepatic/Biliary/Pancreatic, and 4 Dosage and Administration).
Renal Insufficiency
No pharmacokinetic studies have been conducted in renally impaired patients. However, the renal excretion of ambrisentan is minimal, therefore renal impairment should not significantly increase exposure to ambrisentan.
11 Storage, Stability and Disposal
Store between 15-30°C.
12 Special Handling Instructions
There are no special handling instructions.
Part 2 : Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance (s): ambrisentan
Chemical name: (+)-(2S)-2-[(4,6-dimethylpyrimidin-2-yl)oxy]-3-methoxy-3,3-diphenylpropanoic acid
Molecular formula and molecular mass: C22H22N2O4, 378.42
Structural formula:
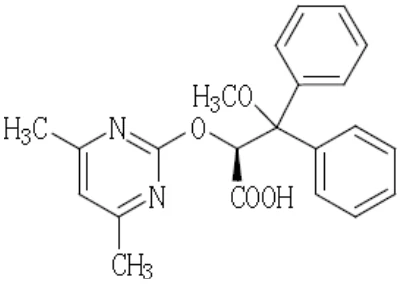
Physiochemical properties: Ambrisentan is a white to off-white, crystalline solid. It is a carboxylic acid with a pKa of 4.0. Ambrisentan is practically insoluble in water and in aqueous solutions at low pH. Solubility increases in aqueous solutions at higher pH. In the solid state ambrisentan is very stable, is not hygroscopic, and is not light sensitive.
14 Clinical Trials
14.1 Clinical Trials by Indication
Pulmonary Arterial Hypertension (PAH)
Table 6 - Summary of the Design and Patient Demographics in Pivotal Clinical Trials of Ambrisentan Tablets in Patients with Pulmonary Arterial Hypertension (PAH)
| Study | Trial design | Dosage, route of administration and duration | Study subjects (n = number randomized) | Mean age (Range) | Sex | PAH Etiology n (%) |
|---|---|---|---|---|---|---|
| Study | Trial design | Dosage, route of administration and duration | Study subjects (n = number randomized) | Mean age (Range) | Sex | PAH Etiology n (%) |
| ARIES-1 | PhaseIII, randomized, double-blind, placebo-controlled, multicentre, multinational | 5 mg and 10 mg tablets taken orally q.d. for 12 weeks | Placebo: n=67 5 mg: n=67 10 mg: n=67 | 50.1 (17-82) | Male: 33 (16.4%) Female: 168 (83.6%) | IPAH*: 126 (62.7%) Non-IPAH: 75 (37.3%) |
| ARIES-2 | PhaseIII, randomized, double-blind, placebo-controlled, multicentre, multinational | 2.5 mg and 5 mg tablets taken orally q.d. for 12 weeks | Placebo: n=65 2.5 mg: n=64 5 mg: n=63 | 50.9 (20-81) | Male: 49 (25.5%) Female: 143 (74.5%) | IPAH*: 125 (65.1%) Non-IPAH: 67 (34.9%) |
| PAMBITION | PhaseIII/IV, randomized, double-blind, active-controlled, multicentre, multinational | ambrisentan 10 mg + tadalafil 40 mg, ambrisentan 10 mg, or tadalafil 40 mg taken orally q.d. Ambrisentan was initiated at 5 mg for 8 weeks and tadalafil at 20 mg for 4 weeks, up-titrated if tolerated | Combination ambrisentan + tadalafil: n=302 Ambrisentan monotherapy: n=152 Tadalafil monotherapy: n=151 | 55.7 (18-75) | Male: 144 (24 %) Female: 461 (76 %) | IPAH*: 330 (54.6%) Non-IPAH: 274 (45.4%) |
*IPAH = idiopathic PAH
Ambrisentan Tablets Monotherapy for the Treatment of PAH
Two randomised, double-blind, multi-centre, placebo controlled, Phase III pivotal studies were conducted (ARIES-1 and ARIES-2). The design and patient demographics are shown in Table 6. In both studies, ambrisentan tablets was added to patients’ supportive/background medication, which may have included a combination of digoxin, anticoagulants, diuretics, oxygen and vasodilators (calcium channel blockers, ACE inhibitors). The primary study endpoint was 6-minute walk distance (6MWD). In addition, clinical worsening, WHO functional class, Borg Dyspnea Index and SF-36 Health Survey were assessed.
Non-IPAH was predominately associated with connective tissue disease, and a few percent associated with anorexigen use or HIV infection. The majority of patients had WHO functional Class II (38%) or Class III (55%) symptoms.
Ambrisentan Tablets in Combination with Tadalafil for the Treatment of PAH
The effect of initial combination therapy with ambrisentan tablets and tadalafil was investigated in a multicenter, double-blind, active-controlled study that compared the combination of ambrisentan tablets and tadalafil to ambrisentan tablets or tadalafil monotherapy in patients with WHO functional class II–III PAH. The study enrolled 610 patients; 605 patients received at least one dose of study drug and 500 met the criteria for the primary efficacy analysis. Patients were randomized 2:1:1 to once daily ambrisentan tablets 10 mg + tadalafil 40 mg, ambrisentan tablets 10 mg, or tadalafil 40 mg.
Ambrisentan tablets were initiated at 5 mg for 8 weeks and tadalafil at 20 mg for 4 weeks, then each was up-titrated if tolerated. In the primary efficacy analysis, 226 patients (89%) treated with ambrisentan tablets+ tadalafil had an up-titration of the tadalafil dose from 20 to 40 mg, and 220 (87%) patients had an up-titration of the ambrisentan tablets dose from 5 mg to 10 mg.
The primary study endpoint was time to first clinical failure event. Secondary endpoints were change in NT-pro-BNP, percentage of patients with satisfactory clinical response, and change from baseline 6MWD, all assessed at Week 24 (see 10 Clinical Pharmacology).
Patients enrolled in the study had idiopathic PAH (53%), heritable PAH (3%), or PAH associated with connective tissue diseases, congenital heart disease, HIV infection, or drugs or toxins (APAH, 44%). Median time from diagnosis to first study drug administration was 22 days. Approximately 31% and 69% of patients were in WHO functional class II and III, respectively. The mean patient age was 54.4 years (32% were ≥65 years old). Most patients were white (90%) and female (78%); 46% were North American. For the primary efficacy analysis, median exposure to combination treatment was 534 days.
Results of Ambrisentan Tablets Monotherapy for the Treatment of PAH
The primary endpoint defined for these studies was improvement in exercise capacity assessed by change from baseline in 6MWD at 12 weeks. In both studies, treatment with ambrisentan tablets resulted in a statistically significant improvement in 6MWD for each dose of ambrisentan tablets as shown in Table 7. The improvement in exercise capacity was evident after 4 weeks of treatment and was maintained at week 12 of the double-blind treatments as illustrated in Figure 1.
Table 7 – Changes from Baseline in 6-minute Walk Distance (metres) at Week 12 in Phase III studies (Idiopathic and Non-Idiopathic PAH Patients: see also Table 11)
| ARIES-1 | ARIES-2 | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Placebo (N=67) | 5 mg (N=67) | 10 mg (N=67) | Placebo (N=65) | 2.5 mg (N=64) | 5 mg (N=63) | ||||||||||||||||
| Baseline | 341.9 ± 73.47 | 339.6 ± 76.68 | 341.5 ± 78.28 | 342.7 ± 85.93 | 347.3 ± 83.81 | 355.3 ± 84.45 | |||||||||||||||
| Mean change from baseline | -7.8 ± 78.88 | 22.8 ± 82.98 | 43.6 ± 65.91 | -10.1 ± 93.79 | 22.2 ± 82.67 | 49.4 ± 75.36 | |||||||||||||||
| Median change from baseline | 0.5 | 21.1 | 32.5 | -3.5 | 27.5 | 40.0 | |||||||||||||||
| Placebo adjusted mean change from baseline | 30.6 | 51.4 | 32.3 | 59.4 | |||||||||||||||||
| 95% CI | 2.9, 58.3 | 26.6, 76.2 | 1.5, 63.1 | 29.6, 89.3 | |||||||||||||||||
| p-value† | 0.008 | <0.001 | 0.022 | <0.001 | |||||||||||||||||
Mean ± standard deviation
† p-values are Wilcoxon rank sum test comparisons of ambrisentan tablets to placebo at Week 12 stratified by idiopathic PAH and non-idiopathic PAH patients
Figure 1 Mean Change in 6-minute Walk Distance (Phase III Studies) in Idiopathic and Non-Idiopathic PAH Patients
| ARIES-1 |
|---|
60 Placebo 45 5 mg 10 mg 30 15 0 -15 -30 Baseline Week 4 Week 8 Week 12 |
| ARIES-2 |
60 Placebo 45 2.5 mg 5 mg 30 15 0 -15 -30 Baseline Week 4 Week 8 Week 12 |
Mean change from baseline in 6-minute walk distance in the placebo and ambrisentan tablets groups Values are expressed as mean ± standard error of mean.
Symptoms of PAH were assessed using Borg Dyspnea Index (BDI), WHO functional class and SF-36 Health Survey physical functioning scale. Treatment with ambrisentan tablets led to statistically significant improvements in BDI at week 12 (Table 8). Improvements in the physical functioning scale (SF-36) were also observed, however, were not statistically significant.
Table 8 Summary of Secondary Endpoints from Study ARIES-1 and ARIES-2 at 12 Weeks (Population ITT)
| ARIES-1 | ARIES-2 | ||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Placebo | Ambrisentan 5 mg | Ambrisentan 10 mg | Placebo | Ambrisentan 2.5 mg | Ambrisentan 5 mg | ||||||||||||||||||||||||
| Change in | Change from | 0.0 | -0.3 | -0.9 | 0.8 | -0.2 | -0.4 | ||||||||||||||||||||||
| Borg Dyspnea Index | baseline to Week 12 | (-0.55, 0.54) | (-0.79, 0.16) | (-1.3, -0.41) | (0.17, 0.54) | (-0.74, 0.34) | (-0.87, 0.14) | ||||||||||||||||||||||
| (BDI) | Comparison | -0.3 | -0.9 | -1.0 | -1.2 | ||||||||||||||||||||||||
| vs placebo, | (-1.0, 0.4) | (-1.6, -0.2) | (-1.9, -0.2) | (-2.0, -0.4) | |||||||||||||||||||||||||
| point estimate | p=0.316 | p=0.002 | p=0.046 | p=0.040 | |||||||||||||||||||||||||
| (95% CI) | - | + | + | + | |||||||||||||||||||||||||
| Change in | Improved | 16 | 19 (28.4%) | 20 (29.9%) | 11 | 10 (15.6%) | 9 (14.3%) | ||||||||||||||||||||||
| WHO | (23.9%) | (16.9%) | |||||||||||||||||||||||||||
Class, N (%) | |||||||||||||||||||||||||||||
| Deteriorated | 11 (16.4%) | 1 (1.5%) | 3 (4.5%) | 12 (18.5%) | 3 (4.7%) | 2 (3.2%) | |||||||||||||||||||||||
| Comparison | p=0.0726 | p=0.0957 | p= 0.2058 | p=0.1872 | |||||||||||||||||||||||||
| with placebo1 | - | - | - | - | |||||||||||||||||||||||||
| Change in | Change from | 1.82 | 1.88 (8.68) | 4.79 (7.90) | -0.15 | 3.78 (7.63) | 2.97 (7.79) | ||||||||||||||||||||||
| SF-36 | baseline, | (9.25) | (7.29) | ||||||||||||||||||||||||||
| Physical | Mean (SD) | ||||||||||||||||||||||||||||
| component summary | |||||||||||||||||||||||||||||
| Comparison with placebo | p=0.992 - | p=0.056 - | 0.005 + | 0.052 - | |||||||||||||||||||||||||
1 Based on analysis of 7-point change from baseline scale
+ statistically significant result, - not statistically significant
Ambrisentan tablets delayed clinical worsening (the measure included a benefit for both death and hospitalization for PAH), although this did not reach a level of statistical significance. Time to clinical worsening of PAH was defined as the time from randomization to the first occurrence of death, lung transplantation, hospitalization for PAH, atrial septostomy, study discontinuation due to the addition of other PAH therapeutic agents, or study discontinuation due to two or more early escape criteria (see Table 9).
Table 9 Summary of Clinical Worsening of PAH Events from Study ARIES-1 and ARIES-2 at 12 Weeks (Population ITT)
| ARIES-1 | ARIES-2 | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Treatment Group Event n (%) | Placebo (N=67) | Ambrisentan 5 mg (N=67) | Ambrisentan 10 mg (N=67) | Placebo (N=65) | Ambrisentan 2.5 mg (N=64) | Ambrisentan5 mg (N=63) | |||||||
| Death | 2 (3.0) | 1 (1.5) | 1 (1.5) | 3 (4.6) | 2 (3.1) | 0 (0.0) | |||||||
| Lung transplantatio n | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||||
| Hospitalization for PAH | 2 (3.0) | 2 (3.0) | 2 (3.0) | 9 (13.8) | 3 (4.7) | 2 (3.2) | |||||||
| Atrial septostomy | 0 (0.00) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||||
| Study discontinuatio n due to addition PAH treatment | 1 (1.5) | 0 (0.0) | 1 (1.5) | 0 (0.0) | 0 (0.0) | 0 (0.0) | |||||||
| Escape criteria | 3 (4.5) | 0 (0.0) | 2 (3.0) | 7 (10.8) | 2 (3.1) | 1 (1.6) | |||||||
| Total subjects with ≥1 | 6 (9.0) | 3 (4.5) | 3 (4.5) | 14 (21.5) | 3 (4.7) | 3 (4.8) | |||||||
p-value (ambrisentan vs placebo)* | 0.4925 | 0.4925 | 0.008 | 0.008 | |||||||||
*Fisher exact test comparison to placebo
In the ARIES studies, those patients with WHO functional class II symptoms at baseline had a mean BDI of 2.98, a mean 6MWD of 375 m; 47% had a 6MWD of more than 400 m. Those with WHO functional class III symptoms had a mean BDI of 4.38 and a mean 6MWD of 330 m at baseline.
In patients with class II and class III symptoms, increases in mean 6MWD were observed with 5 mg and 10 mg ambrisentan tablets compared to placebo after 12 weeks treatment (Table 10). Improvement in secondary endpoints also supported efficacy in both WHO functional class II and class III patients.
Table 10 Improvement in 6MWD at Week 12 in Phase III Studies in patients with WHO Functional Class II symptoms or WHO Functional Class III symptoms (Population ITT)
| ARIES-1 | ARIES-2 | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| Placebo | Ambrisentan Tablets 5 mg | Ambrisentan Tablets 10 mg | Placebo | Ambrisentan Tablets 2.5 mg | Ambrisentan Tablets 5 mg | ||||||
WHO Class II | Change in 6MWD from baseline to Week 12, mean (95% CI) | -0.3 (-19.3, 18.7) | +26.6 (-1.0, 54.2) | +43.4 (17.6, 69.2) | -7.3 (-45.9, 31.4) | +37.0 (9.1,64.9) | +61.4 (31.3, 91.5) | ||||
Placebo-Adjusted improvement in 6MWD, mean (95% CI) | 27.0 (-4.8, 58.7) p=0.0460 | 43.7 (12.8, 74.7) p=0.0072 | +44.2 (-1.1, 89.6) p=0.0624 | +68.6 (21.5, 115.8) p=0.0104 | |||||||
WHO Class III | Change in 6MWD from baseline to Week 12, mean (95% CI) | -15.2 (-45.0, 14.5) | +18.7 (-5.8, 43.3) | +42.2 (21.0, 63.4) | -15.2 (-48.3, 17.8) | +6.2 (-26.2, 38.7) | +38.3 (11.7, 64.9) | ||||
| Placebo-Adjusted improvement in 6MWD, | +34.0 (-4.1, 72.1) p=0.0624 | +57.4 (20.5, 94.3) p=0.0187 | 21.4 (-24.8, 67.7) p=0.4500 | 53.5 (11.2, 95.8) p=0.0217 | |||||||
A summary of the 6-Minute Walk Distance (6MWD) change from baseline to Week 12 is provided in Table 11.
Table 11 Summary of 6-Minute Walk Distance Change from Baseline to Week 12 by PAH Stratification using LOCF (Population: ITT)
| ARIES-1 | ARIES-2 | |||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ARIES-1 | ARIES-2 | |||||||||||||||||||||||
| Treatment Group | Placebo | Ambrisentan Tablets 5 mg | Ambrisentan Tablets 10 mg | Placebo | Ambrisen0tan Tablets 2.5 mg | Ambrisentan Tablets 5 mg | ||||||||||||||||||
| Treatment Group | Placebo | Ambrisentan Tablets 5 mg | Ambrisentan Tablets 10 mg | Placebo | Ambrisen0tan Tablets 2.5 mg | Ambrisentan Tablets 5 mg | ||||||||||||||||||
| IPAH | ||||||||||||||||||||||||
| Change from baseline to Week 12 | N | 43 | 42 | 41 | 42 | 42 | 41 | |||||||||||||||||
| Mean (SD) | -6.3 (82.14) | 36.6 (85.42) | 50.6 (58.22) | -20.6 (101.23) | 35.7 (67.97) | 55.1 (86.58) | ||||||||||||||||||
| Comparison versus placebo | Point estimate | 42.9 | 56.9 | 56.3 | 75.7 | |||||||||||||||||||
| p-value1 | 0.0053 | 0.0011 | 0.005 | <0.001 | ||||||||||||||||||||
| Non-IPAH | ||||||||||||||||||||||||
| Change from baseline to Week 12 | N | 24 | 25 | 26 | 23 | 22 | 22 | |||||||||||||||||
| Mean (SD) | -10.6 (74.32) | -0.4 (74.69) | 32.4 (76.38) | 9.1 (76.77) | -3.5 (102.10) | 38.6 (47.96) | ||||||||||||||||||
| Comparison versus placebo | Point estimate | 10.2 | 43.0 | -12.6 | 29.5 | |||||||||||||||||||
| p-value1 | 0.4965 | 0.0487 | 1.000 | 0.170 | ||||||||||||||||||||
1Wilcoxon rank sum test stratified by IPAH and non-IPAH subjects
Results of Ambrisentan Tablets in Combination with Tadalafil for the Treatment of PAH
Time to Clinical Failure
Time to clinical failure of PAH was a composite endpoint defined as time to the first occurrence of death (all-cause), hospitalization for worsening PAH, disease progression, or unsatisfactory long-term clinical response. Hospitalization for worsening PAH was defined as any hospitalization for worsening PAH, lung or heart/lung transplant, atrial septostomy, or initiation of parenteral prostanoid therapy. Disease progression was defined as >15% decrease from baseline in 6MWD combined with WHO functional class III or IV symptoms (at 2 consecutive post-baseline visits separated by ≥14 days). Unsatisfactory long term clinical response was defined as any reduction in 6MWD below baseline combined with an assessment of functional class III status measured at visits 6 months apart.
Patients treated with ambrisentan tablets + tadalafil experienced a significant reduction in risk of clinical failure versus patients treated with ambrisentan tablets monotherapy (p=0.0004) or tadalafil monotherapy (p=0.0045). The reduction in risk of a clinical failure event was 52% (HR=0.48, 95% CI: 0.31, 0.72) on combination therapy versus ambrisentan tablets monotherapy, and 47% (HR=0.53, 95% CI: 0.34, 0.83) versus tadalafil monotherapy. The Kaplan-Meier plots of time to clinical failure for combination therapy versus each monotherapy are shown in Figure 2; the summary of primary endpoint events is shown in Table 12.
Figure 2 Time to Clinical Failure, Ambrisentan Tablets + Tadalafil Combination Therapy versus Ambrisentan Tablets or Tadalafil Monotherapy (Adjudicated) in the AMBITION Study
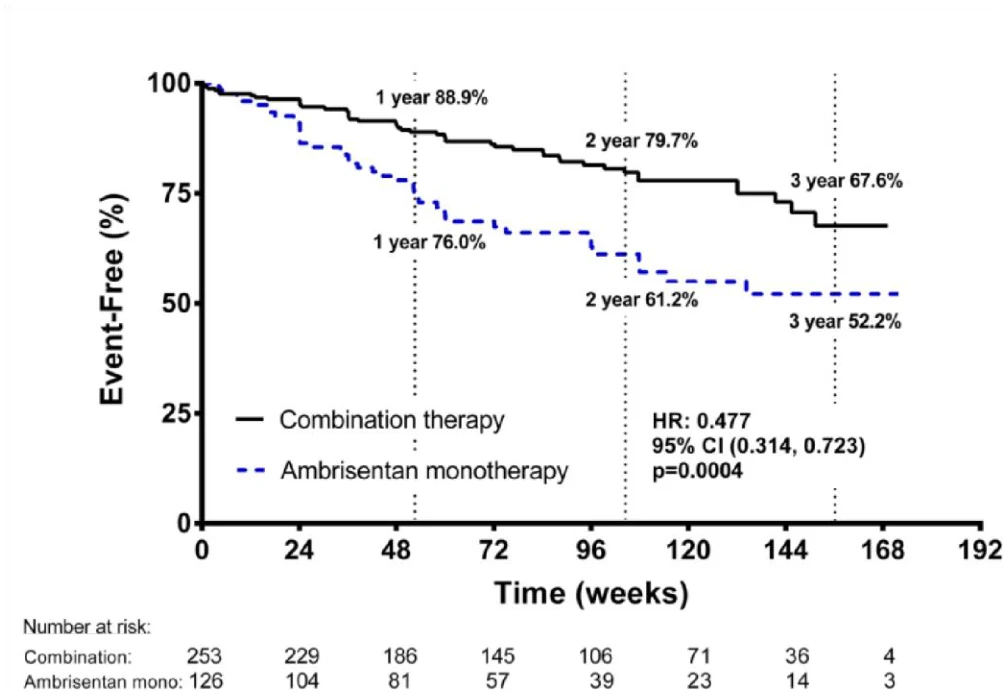
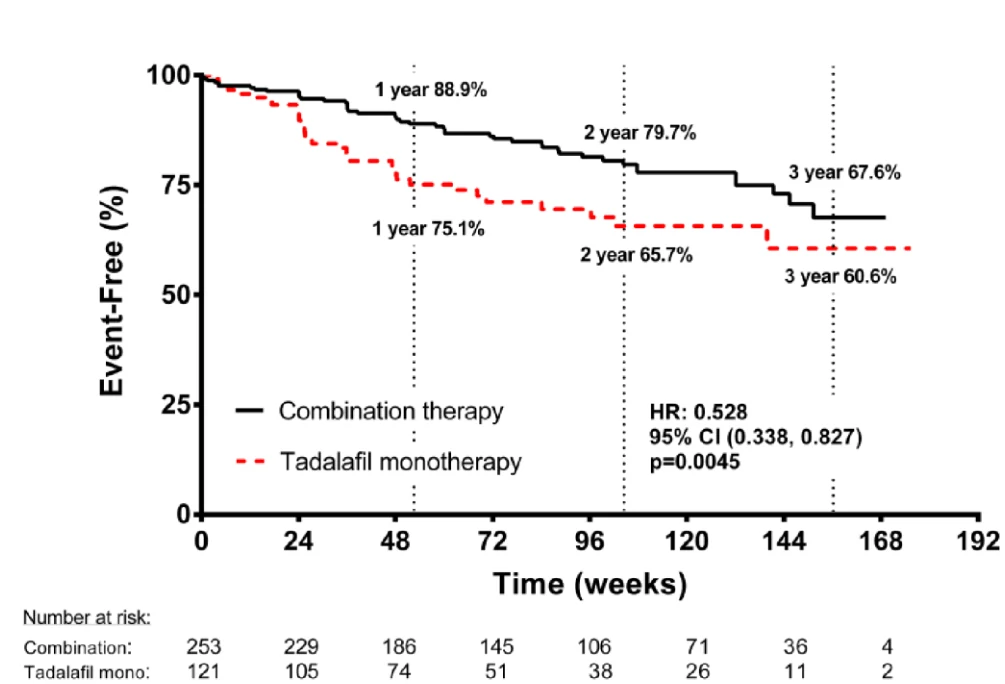
Time from randomization to first clinical failure with Kaplan-Meier estimates of the proportions of failures; p-values shown are the log-rank comparisons of ambrisentan tablets + tadalafil combination therapy to the individual monotherapy.
Table 12 Summary of Primary Endpoint Events (Adjudicated) in the AMBITION Study
Ambrisentan Tablets + Tadalafil (N=253) n (%) | Ambrisentan Tablets Monotherapy (N=126) n (%) | Tadalafil Monotherapy (N=121) n (%) | ||||||
|---|---|---|---|---|---|---|---|---|
| Component as First Clinical Failure Event | ||||||||
| Death (All-Cause) | 9 (4%) | 2 (2%) | 6 (5%) | |||||
| Hospitalization for Worsening PAH | 10 (4%) | 18 (14%) | 12 (10%) | |||||
| Disease Progression | 10 (4%) | 12 (10%) | 4 (3%) | |||||
| Unsatisfactory Long-term Clinical Response | 17 (7%) | 11 (9%) | 12 (10%) | |||||
The results for analyses of time to adjudicated clinical failure and to the first of each component of clinical failure are shown in Figure 3.
Figure 3 Analysis of Adjudicated Events in the AMBITION Study
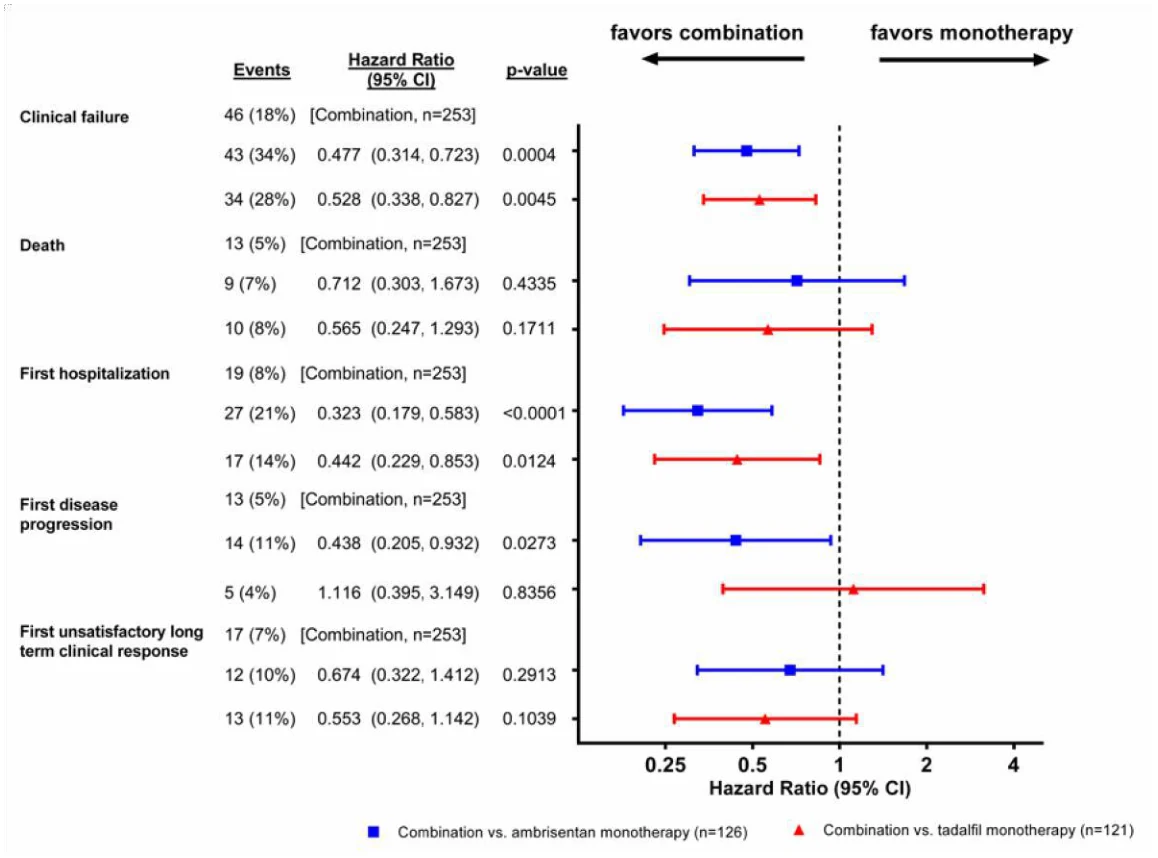
Efficacy of initial combination treatment with ambrisentan tablets + tadalafil on time to clinical failure was seen across the following subgroups of interest: etiology of PAH (IPAH/HPAH and non-IPAH, Baseline WHO FC (II, III), region (North America, rest of world (predominantly European subjects)),
Baseline age group (<65, ≥ 65 years), Baseline age group above or below study median age, sex, and Baseline 6MWD above or below study median 6MWD. Each subgroup analysis showed a reduction in risk with combination therapy relative to the individual monotherapies in all subgroups, with the exception of the male subgroup, in which reduction in risk was not observed with combination therapy relative to tadalafil monotherapy. This may be a statistical artifact due to the relatively low number of male participants (n=122) in the study.
Supportive analyses of time to first adjudicated clinical worsening event (death, hospitalization for worsening PAH, and disease progression) were performed. Patients treated with ambrisentan tablets + tadalafil had a lower risk of having a first adjudicated clinical worsening event at any time from baseline to final assessment visit compared with patients treated with ambrisentan tablets or tadalafil monotherapy. These risk reductions amounted to a statistically significant 56% in comparison with ambrisentan monotherapy (HR=0.443, 95% CI: 0.279, 0.704, p=0.0004), and a statistically non-significant 39% in comparison with tadalafil monotherapy (HR=0.611, 95% CI: 0.364, 1.028, p=0.0607).
Clinical Response
Satisfactory clinical response at Week 24 was a composite secondary endpoint defined as ≥10% improvement in 6MWD compared to baseline, improvement to or maintenance of WHO functional class I or II symptoms, and no events of clinical worsening prior to or at the Week 24 visit. The percentage of patients achieving satisfactory clinical response at Week 24 in the combination therapy group (39%) was significantly greater than in the tadalafil monotherapy group (27%, p=0.0321, odds ratio 1.723, 95% CI: 1.047, 2.833). The difference in satisfactory clinical response between combination therapy and ambrisentan tablets monotherapy (31%, p=0.1518, odds ratio 1.424, 95% CI: 0.878, 2.308) was not statistically significant.
Exercise Ability
The observed improvement from baseline in median 6MWD at Week 24 was higher with combination therapy (from 357.0 m to 414.0 m) than with ambrisentan tablets monotherapy (from 368.5 m to 407.0 m) or with tadalafil monotherapy (from 363.3 m to 392.0 m). Statistical analysis using imputed data showed that the difference between median change in the combination therapy group (49.0m, 95% CI: 39.0, 57.5) and the ambrisentan tablets monotherapy group (27.0 m, 95% CI: 12.5, 38.0) was statistically significant (p=0.0005), and so was the difference with the tadalafil monotherapy group (22.7 m, 95% CI: 16.5, 35.5; p=0.003).
Figure 4 Median Change from Baseline in 6-Minute Walk Distance (meters) in the AMBITION Study
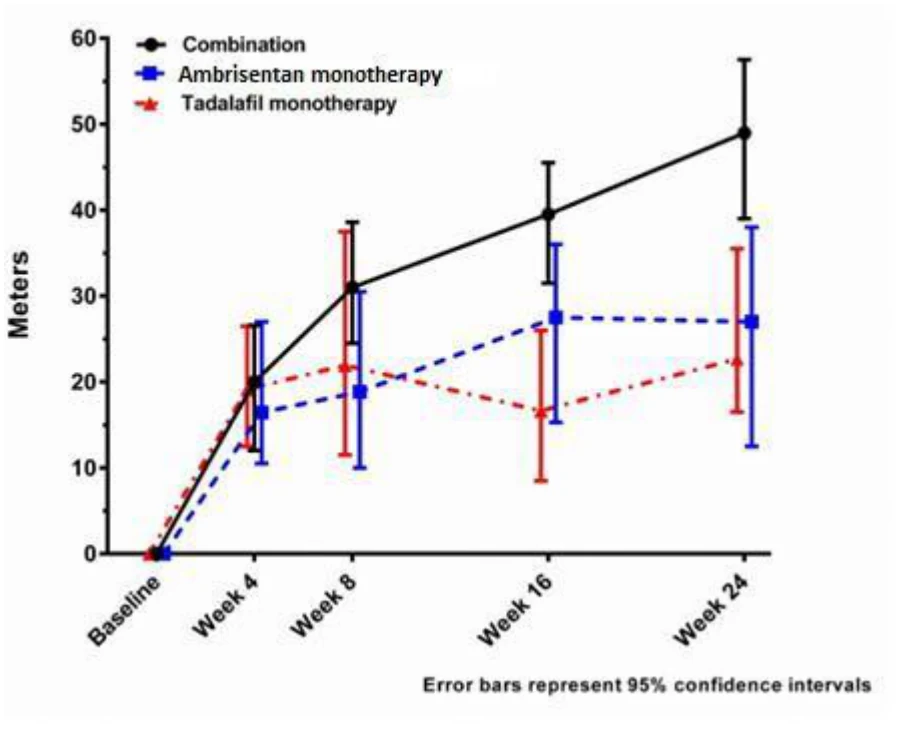
Hepatic Safety
Hepatic function was assessed in clinical studies. In ARIES 1 and 2, there were no cases of aminotransferase abnormalities >3x the upper limit of normal (ULN) in 262 patients receiving ambrisentan tablets compared with three cases (out of 132) in patients receiving placebo (2.3%). The cumulative incidence of serum aminotransferase abnormalities >3x ULN in all Phase II and III (including extension) studies was 3.5% (17 of 483 subjects over a mean exposure duration of 79.5 weeks). In the ARIES-E open label long term extension study of ARIES-1 and ARIES-2 (N=383), the 2 year risk of developing serum aminotransferase elevations >3x ULN in patients treated with ambrisentan tablets was 3.9%. In the AMBITION study, in a subset of patients without left ventricular dysfunction, the incidence of serum aminotransferase (ALT and/or AST) abnormalities >3x ULN when ambrisentan tablets was used in combination with tadalafil was 4% (10 of 253 patients), versus 2% (2 of 126 patients) when ambrisentan tablets was used in monotherapy, versus 3% (3 of 121 patients when tadalafil was used in monotherapy. Incidence rates were similar when considering populations with left ventricular dysfunction.
14.2 Comparative Bioavailability Studies
A randomized, two-treatment, two-period single-dose (1 x 10 mg) crossover bioequivalence study of M-AMBRISENTAN (Mantra Pharma Inc.) and PrVOLIBRIS® (GlaxoSmithKline Inc.) was performed in 26 healthy adult male subjects under fasting conditions. The results from 22 subjects that were included in the pharmacokinetic and statistical analyses are summarized in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Ambrisentan (1 x 10 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90 % Confidence Interval |
AUCT (ng/mL) | 9930.52 10157.31 (22.65) | 9928.40 10038.30 (15.50) | 100.0 | 95.6 – 104.7 |
AUCI (ng/mL) | 10432.48 10656.34 (21.86) | 10345.50 10464.08 (15.87) | 100.8 | 96.5 – 105.4 |
CMAX (ng hr/mL) | 1317.32 1337.76 (17.81) | 1254.64 1278.84 (19.56) | 105.0 | 97.3 – 113.3 |
TMAX3 (h) | 2.38 (0.75 – 4.00) | 3.00 (0.75 – 5.00) | ||
T½ 4 (h) | 9.87 (19.50) | 9.57 (17.03) | ||
1 M-AMBRISENTAN (ambrisentan) tablets, 10 mg (Mantra Pharma Inc.).
2 PrVOLIBRIS© (ambrisentan) tablets, 10 mg (GlaxoSmithKline Inc.).
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
15 Microbiology
No microbiological information is required for this drug product.
16 Non-Clinical Toxicology
General Toxicology:
The principal findings in repeat dose toxicity studies in mice and rats with ambrisentan are in part attributed to exaggerated pharmacology and include effects in the nasal cavity and testes. Repeat dose studies in the dog reveal ambrisentan tablets to be well tolerated with findings limited to fundic glandular atrophy and clinical signs of audible breathing and gastrointestinal disturbance. Deaths or findings resulting in early sacrifice of animals attributed to oral administration of ambrisentan tablets occurred in repeat-dose toxicity studies in rats at ≥ 100 mg/kg/day and in dogs at 1500 mg/kg/day. An increased mortality rate also occurred in 2-year carcinogenicity studies in rats at 30/20 and 60/40 mg/kg/day (initial daily dose of 30 mg/kg/day subsequently lowered to 20 mg/kg/day, and 60 mg/kg/day subsequently lowered to 40 mg/kg/day) and mice at 250/150 mg/kg/day (initial daily dose of 250 mg/kg/day subsequently lowered to 150 mg/kg/day).
Inflammation and changes in the nasal cavity epithelium and/or turbinates have been seen with chronic administration of ambrisentan tablets and other endothelin receptor antagonists (ERAs) to rodents and, to a lesser extent, dogs.
Genotoxicity
The genotoxicity of ambrisentan was assessed in a comprehensive battery of in vitro and in vivo studies. Ambrisentan was clastogenic in human lymphocytes in vitro both in the presence and absence of metabolic activation. Ambrisentan was not mutagenic to Salmonella typhimurium, did not elicit unscheduled DNA synthesis in rat liver, and was not clastogenic in an in vivo micronucleus study conducted in male rats.
Carcinogenicity
There was no evidence of carcinogenic potential in 2 year oral daily dosing studies in rats and mice. There was a small increase in mammary fibroadenomas, a benign tumor, in male rats at the highest dose only.
Reproductive and Developmental Toxicity
The development of testicular tubular atrophy and sterility in male animals has been linked to the chronic administration of ERAs, including ambrisentan, to rodents. Testicular tubular atrophy was observed at all dose levels (10 to 300 mg/kg/day) in oral fertility studies with male rats that was not reversible after 13 or 20 weeks following cessation of dosing. Reduced fertility and morphologic effects on sperm only occurred at 300 mg/kg/day and were reversible. No effects on sperm count or sperm motility were observed. Testicular tubular atrophy (focal/multifocal or diffuse) was also observed in repeat dose studies in rats and mice. There were no significant effects on fertility or embryofetal development in female rats dosed up to the time of implantation.
Teratogenicity is a class effect of ERAs. The effect of ambrisentan on embryo-fetal development has been assessed in rats and rabbits after oral dose administration on gestation days 6-17 and 6-18, respectively. In both species, abnormalities of the lower jaw, tongue, and/or palate were consistently observed at all dose levels. Additionally, interventricular septal defects, trunk vessel defects, thyroid and thymus abnormalities, ossification of the basisphenoid bone, and the occurrence of the umbilical artery located on the left side of the urinary bladder instead of the right side and heart and associated blood vessel abnormalities were seen in the rabbit study.
Juvenile Toxicity
In a juvenile rat study, oral administration of ambrisentan once daily during postnatal day (PND) 7 to 62 decreased brain weight -4% in males and females with no brain morphologic effects at 20 mg/kg/day, after a period of breathing sounds which occurred at doses of 4 mg/kg/day and above (1.5 to 6.4 times higher than the maximum recommended human adult dose of 10 mg, based on AUC). In two separate respiratory function juvenile rat studies, 20 mg/kg/day of ambrisentan administered on PND 7 to 26 or PND 7 to 36 evoked decreases in brain weight (-3% to -8%), and also caused breathing sounds (a singular audible click), irregular respiratory function, apnea and hypoxia starting 10 days after dosing, and continuing two days after treatment stopped, with no detection of these effects at one month after dose interruption. There were no neurobehavioral changes observed at the end of treatment and one month after dose interruption, and a morphometric assessment of changes to the pharynx and larynx was inconclusive. Although the mechanisms by which ambrisentan reduces brain weight of juvenile rats have not been fully elucidated, it is plausible that this effect is mediated by chronic hypoxia that may be associated with mechanically induced apnea originating from pharyngeal dysmorphogenesis occurring during postnatal pharyngeal development. The clinical relevance of this finding in humans is unknown; however, this postnatal time frame would likely correlate to human pharyngeal development from 0 to 3 years of age. Safety and efficacy of ambrisentan tablets have not been established in patients under 18 years of age. M-AMBRISENTAN should therefore not be used in this age group.
17 Supporting Product Monographs
- 1. VOLIBRIS© (tablets, 5 mg and 10 mg), submission control 299437, Product Monograph,
GlaxoSmithKline Inc. (2025-12-02).