


Product Monograph - M-Amoxi Clav
RECENT MAJOR LABEL CHANGES
| 3 SERIOUS WARNINGS AND PRECAUTIONS BOX | 06/2024 |
|---|---|
| 7 Warnings and Precautions, Immune | 06/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES .............................................................................................. 2
TABLE OF CONTENTS ................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ........................................................................ 4
1 INDICATIONS ................................................................................................................. 4
1.1 Pediatrics .............................................................................................................. 4
1.2 Geriatrics .............................................................................................................. 4
2 CONTRAINDICATIONS .................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ............................................................... 5
4 DOSAGE AND ADMINISTRATION ................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ..................................................... 5
4.3 Reconstitution ...................................................................................................... 9
4.4 Administration ................................................................................................... 10
4.5 Missed Dose ....................................................................................................... 10
5 OVERDOSAGE .............................................................................................................. 10
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................. 11
7 WARNINGS AND PRECAUTIONS ................................................................................... 11
7.1 Special Populations ............................................................................................ 14
7.1.1 Pregnant Women ............................................................................................... 14
7.1.2 Breast-feeding .................................................................................................... 14
7.1.3 Pediatrics ............................................................................................................ 14
8 ADVERSE REACTIONS ................................................................................................... 14
8.2 Clinical Trial Adverse Reactions .......................................................................... 14
8.2.1 Clinical Trial Adverse Reactions – Pediatrics ....................................................... 14
8.5 Post-Market Adverse Reactions ......................................................................... 15
9 DRUG INTERACTIONS .................................................................................................. 16
9.4 Drug-Drug Interactions ....................................................................................... 16
9.5 Drug-Food Interactions ...................................................................................... 17
9.6 Drug-Herb Interactions ...................................................................................... 17
9.7 Drug-Laboratory Test Interactions ..................................................................... 17
10 CLINICAL PHARMACOLOGY .......................................................................................... 17
10.1 Mechanism of Action ......................................................................................... 17
10.3 Pharmacokinetics ............................................................................................... 17
11 STORAGE, STABILITY AND DISPOSAL ........................................................................... 18
12 SPECIAL HANDLING INSTRUCTIONS ............................................................................. 19
PART II: SCIENTIFIC INFORMATION ......................................................................................... 20
13 PHARMACEUTICAL INFORMATION .............................................................................. 20
14 CLINICAL TRIALS .......................................................................................................... 21
14.2 Comparative Bioavailability Studies ................................................................... 21
15 MICROBIOLOGY ........................................................................................................... 24
16 NON-CLINICAL TOXICOLOGY ........................................................................................ 28
17 SUPPORTING PRODUCT MONOGRAPHS ...................................................................... 33
PATIENT MEDICATION INFORMATION .................................................................................... 34
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
M-AMOXI CLAV (amoxicillin / clavulanate potassium) is indicated for the treatment of the following infections when caused by M-AMOXI CLAV-susceptible strains of the designated bacteria:
- Sinusitis when caused by β-lactamase producing strains of H. influenzae or Moraxella (Branhamella) catarrhalis.
- Otitis Media when caused by β-lactamase producing strains of H. influenzae or Moraxella (Branhamella) catarrhalis.
- Lower Respiratory Tract Infections when caused by β-lactamase producing strains of H. influenzae, K. pneumoniae, S. aureus or Moraxella (Branhamella) catarrhalis.
- Skin and Soft Tissue Infections when caused by β-lactamase producing strains of S. aureus.
- Urinary Tract Infections when caused by β-lactamase producing strains of E. coli.
While M-AMOXI CLAV is indicated only for the conditions listed above, infections caused by ampicillin (amoxicillin) susceptible organisms are also amenable to M-AMOXI CLAV treatment due to its amoxicillin content. Furthermore, mixed infections caused by organisms susceptible to ampicillin (amoxicillin) and β-lactamase producing organisms susceptible to M-AMOXI CLAV should not require the addition of another antibiotic.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of M-AMOXI CLAV and other antibacterial drugs, M-AMOXI CLAV should be used only to treat infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology data, susceptibility patterns, and local official antibiotic prescribing guidelines, may contribute to the empiric selection of therapy.
1.1 Pediatrics
Pediatrics (< 18): See 4.2 Recommended Dose and Dosage Adjustment, Pediatrics, 7.1.3 Pediatrics.
1.2 Geriatrics
Geriatrics: See 7 WARNINGS AND PRECAUTIONS, Hepatic/Biliary/Pancreatic.
2 CONTRAINDICATIONS
M-AMOXI CLAV is contraindicated in patients:
- with a history of hypersensitivity to the penicillin, or cephalosporin group of β-lactams, or to any ingredients contained in the preparation or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- where infectious mononucleosis is either suspected or confirmed.
- with a previous history of amoxicillin and clavulanate potassium -associated jaundice/hepatic dysfunction.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.2 Recommended Dose and Dosage Adjustment
Pediatrics (3 months and older)
In infants 12 weeks (3 months) of age or older and in children, b.i.d. use of the M-AMOXI CLAV 400 mg formulation is recommended because of a significantly reduced incidence of diarrhea with the b.i.d. regimen (see 8 ADVERSE REACTIONS).
Based on the amoxicillin component, M-AMOXI CLAV should be dosed as follows in patients aged 12 weeks (3 months) and older:
| Infection | Severity | Dosing Regimen | |
|---|---|---|---|
B.I.D.* 200 mg amoxicillin / 28.5 mg Clavulanic Acid*** 400 mg amoxicillin / 57 mg Clavulanic Acid | T.I.D. 125 mg amoxicillin / 31.25 mg clavulanic acid*** 250 mg amoxicillin / 62.5 mg clavulanic acid | ||
| Urinary tract | Mild to moderate | 25 mg/kg/day in divided doses every 12 hours | 20 mg/kg/day in divided doses every 8 hours |
| Skin and Soft Tissue | Severe | 45 mg/kg/day in divided doses every 12 hours | 40 mg/kg/day in divided doses every 8 hours |
Lower Respiratory Tract Sinusitis | 45 mg/kg/day in divided doses every 12 hours | 40 mg/kg/day in divided doses every 8 hours | |
| Infection | Severity | Dosing Regimen | |
|---|---|---|---|
B.I.D.* 200 mg amoxicillin / 28.5 mg Clavulanic Acid*** 400 mg amoxicillin / 57 mg Clavulanic Acid | T.I.D. 125 mg amoxicillin / 31.25 mg clavulanic acid*** 250 mg amoxicillin / 62.5 mg clavulanic acid | ||
| Otitis Media** | 40 mg/kg/day in divided doses every 8 hours | ||
*The bid regimen is recommended as it is associated with significantly less diarrhea.
**Duration of therapy studied and recommended for acute otitis media is 10 days.
***M-AMOXI-CLAV is only available in strengths of 250 mg amoxicillin / 62.5 mg clavulanic acid and of 400 mg amoxicillin / 57 mg clavulanic acid.
The normal duration of treatment was 7 to 10 days. However, in general, treatment should be continued for a minimum of 48 to 72 hours beyond the time that the patient becomes asymptomatic or evidence of bacterial eradication has been obtained. It is recommended that there be at least 10 days treatment for any infection caused by β-hemolytic streptococci to prevent the occurrence of acute rheumatic fever or glomerulonephritis.
The children's dosage should not exceed that recommended for adults. Children weighing more than 38 kg should be dosed according to the adult recommendations (i.e., the usual adult dose is one (1) amoxicillin and clavulanate potassium-500 mg/125 mg tablet every 12 hours. For more severe infections and infections of the lower respiratory tract, the dose should be one (1) amoxicillin and clavulanate potassium-875 mg/125 mg tablet every 12 hours or one (1) amoxicillin and clavulanate potassium-500 mg/125 mg tablet every 8 hours).
Table 1 below may be used as a guide to determine the dosage of oral suspension (125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension or M-AMOXI CLAV (250 mg / 62.5 mg per 5 mL)) according to body weight.
Table 1 Pediatric Dosage Schedule for 125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension and M-AMOXI CLAV 250 mg / 62.5 mg per 5 mL Oral Suspensionsa
| Body Weight | 20 mg/kg/day dosing regimena | 40 mg/kg/day dosing regimena | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Total Daily Doseb | Volume (mL) of Reconstituted Oral Suspension Every 8 Hours | Total Daily Doseb | Volume (mL) of Reconstituted Oral Suspension Every 8 Hours | |||||||||||
| (kg) | (mg) | 125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension | M-AMOXI CLAV (250 mg / 62.5 mg) | (mg) | 125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension | M-AMOXI CLAV (250 mg / 62.5 mg) | ||||||||
05 07 10 12 14 16 18 20 25 30 35 38 | 125 175 250 300 350 400 450 500 625 750 875 950 | 1.3 1.9 2.7 3.2 3.7 4.3 4.8 5.3 6.7 8.0 9.3 10.1 | 0.7 0.9 1.3 1.6 1.9 2.1 2.4 2.7 3.3 4.0 4.7 5.1 | 250 350 500 600 700 800 900 1000 1250 1500 1750 1900 | 2.7 3.7 5.3 6.4 7.5 8.5 9.6 10.7 13.3 16.0 18.7 20.3 | 1.3 1.9 2.7 3.2 3.7 4.3 4.8 5.3 6.7 8.0 9.3 10.1 | ||||||||
a Based on amoxicillin component
b Dosages are expressed in terms of amoxicillin plus clavulanic acid. These two ingredients are in a ratio of 4:1 in both oral suspensions 125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension and M-AMOXI CLAV (250 mg / 62.5 mg).
Twenty (20) mL of reconstituted 125 mg amoxicillin / 31.25 mg clavulanic acid per 5 mL for oral suspension or ten (10) mL of reconstituted M-AMOXI CLAV (250 mg / 62.5 mg per 5 mL) are equivalent to one (1) amoxicillin and clavulanate potassium-500 mg /125 mg tablet.
Table 2 below may be used as a guide to determine the dosage of oral suspension (200 mg amoxicillin / 28.5 mg clavulanic acid per 5 mL for oral suspension or M-AMOXI CLAV (400 mg / 57 mg per 5 mL)) according to body weight.
Table 2 Pediatric Dosage Schedule for 200 mg amoxicillin / 28.5 mg clavulanic acid per 5 mL for oral suspension and M-AMOXI CLAV 400 mg / 57 mg per 5 mL Oral Suspension
| Body Weight | 25 mg/kg/day dosing regimena | 45 mg/kg/day dosing regimena | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Total Daily Doseb | Volume (mL) of Reconstituted Oral Suspension Every 12 Hours | Total Daily Doseb | Volume (mL) of Reconstituted Oral Suspension Every 12 Hours | |||||||||||
| (kg) | (mg) | 200 mg amoxicillin / 28.5 mg clavulanic acid per 5 mL for oral suspension | M-AMOXI CLAV (400 mg / 57 mg) | (mg) | 200 mg amoxicillin / 28.5 mg clavulanic acid per 5 mL for oral suspension | M-AMOXI CLAV (400 mg / 57 mg) | ||||||||
05 07 10 12 14 16 18 20 25 30 35 38 | 143 200 286 343 400 458 515 572 715 858 1001 1087 | 1.6 2.2 3.1 3.8 4.4 5.0 5.6 6.3 7.8 9.4 11.0 11.9 | 0.8 1.1 1.6 1.9 2.2 2.5 2.8 3.1 3.9 4.7 5.5 5.9 | 257 360 514 617 720 822 925 1028 1285 1542 1799 1953 | 2.8 3.9 5.6 6.8 7.9 9.0 10.1 11.3 14.1 16.9 19.7 21.4 | 1.4 2.0 2.8 3.4 3.9 4.5 5.1 5.6 7.0 8.4 9.8 10.7 | ||||||||
a Based on amoxicillin component
b Dosages are expressed in terms of amoxicillin plus clavulanic acid. These two ingredients are in a ratio of 7:1 in both oral suspensions, 200 mg amoxicillin / 28.5 mg clavulanic acid per 5 mL for oral suspension and M-AMOXI CLAV (400 mg / 57 mg per 5 mL)
A calibrated dropper should be used to measure the appropriate volume for dosing.
Pediatrics (Neonates and children aged <12 weeks (3 months))
Due to incompletely developed renal function affecting elimination of amoxicillin in this age group, the recommended dose of M-AMOXI CLAV is 30 mg/kg/day divided q12h, based on the amoxicillin component. Clavulanate elimination is unaltered in this age group. Experience with the 200 mg/5 mL formulation in this age group is limited and, thus, use of the 125 mg/5 mL oral suspension is recommended.
Renal Insufficiency
Dosage adjustment in renal impairment is based on the maximum recommended level of amoxicillin. M-AMOXI CLAV presentations with a 7:1 ratio of amoxicillin: clavulanate (i.e. the M-AMOXI CLAV 400 mg / 57 mg per 5 mL oral suspension) should be used only in patients with a creatinine clearance of more than 30 ml/min.
Pediatrics
| Creatinine clearance > 30 ml/min | No adjustment necessary. |
|---|---|
| Creatinine clearance 10 - 30 ml/min | 15/3.75 mg/kg given twice daily (maximum 500/125 mg twice daily). |
| Creatinine clearance < 10 ml/min | 15/3.75 mg/kg given as a single daily dose (maximum 500/125 mg). |
| Hemodialysis | 15/3.75 mg/kg/day given as a single daily dose. Prior to hemodialysis one additional dose of 15/3.75 mg/kg should be administered. In order to restore circulating drug levels, another dose of 15/3.75 mg/kg should be administered after hemodialysis. |
M-AMOXI CLAV (400 mg/57 mg per 5 mL) oral suspension (7:1 ratio amoxicillin: clavulanate) should only be used in patients with a creatinine clearance of more than 30 ml/min.
4.3 Reconstitution
Reconstitute Powder for Oral Suspension with purified water.
M-AMOXI CLAV (250 mg / 62.5 mg):
The approximate average concentration after reconstitution is 250 mg of amoxicillin (as the trihydrate) and 62.5 mg of clavulanic acid (as the potassium salt) per 5 mL. Measure 85 mL of water and add to the bottle in two portions (42.5 mL each). Shake vigorously after each addition.
| Package size | Reconstituted volume | Amount of water required for the strength of 250 mg / 62.5 mg |
|---|---|---|
| 125 mL bottle | 100 mL | 85 mL |
M-AMOXI CLAV (400 mg / 57 mg):
The approximate average concentration after reconstitution is 400 mg of amoxicillin (as the trihydrate) and 57 mg of clavulanic acid (as the potassium salt) per 5 mL. Measure 62 mL of water and add to the bottle in two portions (31 mL each). Shake vigorously after each addition.
| Package size | Reconstituted volume | Amount of water required for the strength of 400 mg / 57 mg |
|---|---|---|
| 100 mL bottle | 70 mL | 62 mL |
The reconstituted M-AMOXI CLAV (250 mg / 62.5 mg per 5 mL) oral suspension should be stored under refrigeration (2°C to 8°C) and should be used within 10 days. Discard unused suspension after 10 days.
The reconstituted M-AMOXI CLAV (400 mg / 57 mg per 5 mL) oral suspension should be stored under refrigeration (2°C to 8°C) and should be used within 7 days. Discard unused suspension after 7 days (see 11 STORAGE, STABILITY AND DISPOSAL).
4.4 Administration
While M-AMOXI CLAV can be given without regard to meals, absorption of clavulanic acid when taken with food is greater relative to the fasted state. Dosing in the fasted or fed state has minimal effect on the pharmacokinetics of amoxicillin. The safety and efficacy of amoxicillin and clavulanate potassium have been established in clinical trials where amoxicillin and clavulanate potassium was taken without regard to meals.
To minimize potential gastrointestinal intolerance, administer at the start of a meal.
4.5 Missed Dose
If a dose is missed, it should be taken as soon as remembered unless it is almost time for the next dose. The dose should not be doubled to make up for a missed dose.
5 OVERDOSAGE
Activated charcoal may be administered to aid in the removal of unabsorbed drug. General supportive measures are also recommended.
Many patients have been asymptomatic following overdosage or have experienced primarily gastrointestinal symptoms including stomach and abdominal pain, vomiting, and diarrhea. Rash, hyperactivity, or drowsiness have also been observed in a small number of patients. Amoxicillin crystalluria, in some cases leading to renal failure, has been observed (see 7 WARNINGS AND PRECAUTIONS).
In the case of overdosage, discontinue M-AMOXI CLAV treat symptomatically, and institute supportive measures as required. If gastrointestinal symptoms and disturbance of the fluid and electrolyte balances are evident, they may be treated symptomatically. Amoxicillin and clavulanate potassium can be removed from the circulation by haemodialysis. A prospective study of 51 pediatric patients at a poison center suggested that overdosages of less than 250 mg/kg of amoxicillin are not associated with significant clinical symptoms and do not require gastric emptying.
Interstitial nephritis resulting in oliguric renal failure has been reported in a small number of patients after overdosage with amoxicillin. Renal impairment appears to be reversible with cessation of drug administration. High blood levels may occur more readily in patients with impaired renal function because of decreased renal clearance of both amoxicillin and clavulanate. Both amoxicillin and clavulanate are removed from the circulation by hemodialysis.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 3 – Route of Administration, Dosage Forms, Strengths and Non-medicinal Ingredients
Availability of Dosage Forms
Powder for Oral Suspensions:
M-AMOXI CLAV (250 mg / 62.5 mg) is available in bottles of 100 mL (reconstitution volume).
M-AMOXI CLAV (400 mg / 57 mg) is available in bottles of 70 mL (reconstitution volume).
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX.
General
The possibility of superinfections with mycotic or bacterial pathogens should be kept in mind during therapy with M-AMOXI CLAV. If superinfection should occur (usually involving Enterobacter (Aerobacter), Pseudomonas or Candida), the administration of M-AMOXI CLAV should be discontinued and appropriate therapy instituted.
Prolonged use may also occasionally result in overgrowth of non-susceptible organisms.
The occurrence of a morbilliform rash following the use of ampicillin in patients with infectious mononucleosis is well documented. This reaction has also been reported following the use of amoxicillin. A similar reaction would also be expected with M-AMOXI CLAV.
Clostridium difficile-associated disease
Clostridium difficile -associated disease (CDAD) has been reported with the use of many antibacterial agents, including amoxicillin and clavulanate potassium. CDAD may range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea, or symptoms of colitis, pseudomembranous colitis, toxic megacolon,
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Powder for oral suspension M-AMOXI CLAV 250 mg/62.5 mg per 5 mL: Each 5 mL of reconstituted suspension contains 250 mg of amoxicillin as the trihydrate and 62.5 mg of clavulanic acid as the potassium salt (in a ratio of 4:1) M-AMOXI CLAV 400 mg/57 mg per 5 mL: Each 5 mL of reconstituted suspension contains 400 mg of amoxicillin as the trihydrate and 57 mg of clavulanic acid as the potassium salt (in a ratio of 7:1) | Carmellose sodium, citric acid anhydrous, colloidal silica, mannitol, microcrystalline cellulose, silicon dioxide, sodium citrate anhydrous, sucralose, tutti frutti flavour, vanilla flavour and, xanthan gum. |
or perforation of colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur over 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. Clostridium difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated, as surgical intervention may be required in certain severe cases (see 8 ADVERSE REACTIONS).
Cardiovascular
Abnormal prolongation of prothrombin time (increased international normalized ratio (INR)) has been reported in patients receiving amoxicillin and clavulanate potassium and oral anticoagulants. Appropriate monitoring should be undertaken when anticoagulants are prescribed concurrently. Adjustments in the dose of oral anticoagulants may be necessary to maintain the desired level of anticoagulation.
Kounis syndrome (see 7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions).
Hepatic/Biliary/Pancreatic
Transient hepatitis and cholestatic jaundice have been reported rarely. These events have been noted with other penicillins and cephalosporins. Hepatic injury events associated with amoxicillin and clavulanate potassium may be severe, and occur predominantly in males and elderly patients and may be associated with prolonged treatment. These events have been very rarely reported in children. Signs and symptoms usually occur during or shortly after treatment, but in some cases may not become apparent until several weeks after treatment has ceased.
Hepatic toxicity associated with the use of amoxicillin and clavulanate potassium is usually reversible. On rare occasions, deaths have been reported (less than 1 death reported per estimated 4 million prescriptions worldwide). These have generally been cases associated with serious underlying diseases or concomitant medications (see 2 CONTRAINDICATIONS and 8.5 Post-Market Adverse Reactions, Liver).
M-AMOXI CLAV should be used with caution in patients with evidence of hepatic dysfunction.
Immune
Hypersensitivity Reactions
Serious and occasionally fatal hypersensitivity reactions, including:
- angioedema
- anaphylactic/anaphylactoid reactions
- severe cutaneous adverse reactions (SCAR) (e.g., acute generalized exanthematous pustulosis (AGEP), Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS)). These have been reported in patients on penicillin therapy, including M-AMOXI CLAV (amoxicillin / clavulanate potassium).
- Kounis syndrome, a serious allergic reaction that can result in myocardial infarction. Presenting symptoms of such reactions can include chest pain occurring in association with an allergic reaction to amoxicillin-clavulanate.
- Drug-induced enterocolitis syndrome, an allergic reaction with the leading symptom of protracted vomiting (1-4 hours after medicinal product administration), in the absence of allergic skin or respiratory symptoms, has been reported mainly in children receiving amoxicillin-clavulanate. Further symptoms could comprise abdominal pain, lethargy, diarrhea, hypotension or leucocytosis with neutrophilia. In severe cases, drug-induced enterocolitis syndrome can progress to shock.
(See 8.5 Post-Market Adverse Reactions)
Although these reactions are more frequent following parenteral therapy, they have occurred in patients receiving penicillins orally. These reactions are more apt to occur in individuals with a history of sensitivity to multiple allergens. There have been reports of individuals with a history of cephalosporin hypersensitivity who have experienced severe reactions when treated with penicillins. Before initiating therapy with M-AMOXI CLAV, careful inquiry should be made concerning previous hypersensitivity reactions to penicillins, cephalosporins, or other allergens (see 2 CONTRAINDICATIONS).
If an allergic reaction occurs, the administration of M-AMOXI CLAV should be discontinued and appropriate alternative therapy should be instituted. Serious anaphylactic/anaphylactoid reactions require immediate emergency treatment with epinephrine. Oxygen, intravenous steroids and airway management, including intubation should also be used as indicated.
Monitoring and Laboratory Tests
Periodic assessment of renal, hepatic, and hematopoietic function should be made during prolonged therapy with M-AMOXI CLAV.
Renal
Amoxicillin and clavulanate potassium for oral suspension is excreted mostly by the kidney. In renal impairment, dosage adjustments should be made based on the maximum recommended level of amoxicillin (see 4.2 Recommended Dose and Dosage Adjustment, Renal Insufficiency).
In patients with reduced urine output, crystalluria has been observed very rarely, predominantly with parenteral therapy. During the administration of high doses of amoxicillin, it is advisable to maintain adequate fluid intake and urinary output in order to reduce the possibility of amoxicillin crystalluria (see 5 OVERDOSAGE).
Sensitivity/Resistance
Prescribing M-AMOXI CLAV in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and risks the development of drug-resistant bacteria.
Skin
Severe cutaneous adverse reactions (SCAR) have been reported with amoxicillin and clavulanate potassium (see 7 WARNINGS and PRECAUTIONS, Hypersensitivity Reactions).
7.1 Special Populations
7.1.1 Pregnant Women
In a single study in women with preterm, premature rupture of the fetal membranes (pPROM), it was reported that prophylactic treatment with amoxicillin and clavulanate potassium may be associated with an increased risk of necrotising enterocolitis in neonates. Use should be avoided in pregnancy, unless considered essential by the physician.
7.1.2 Breast-feeding
Penicillins (including ampicillin) have been shown to be excreted in human breast milk. It is not known whether clavulanic acid is excreted in breast milk. Caution should be exercised if M-AMOXI CLAV is to be administered to a nursing mother.
7.1.3 Pediatrics
Because of incompletely developed renal function in neonates and young infants, the elimination of amoxicillin may be delayed. Dosing of M-AMOXI CLAV should be modified in pediatric patients younger than 12 weeks (3 months), see 4.2 Recommended Dose and Dosage Adjustment, Pediatrics (Neonates and children aged <12 weeks (3 months)).
8 ADVERSE REACTIONS
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
A U.S./Canadian clinical trial compared a 10-day amoxicillin and clavulanate potassium b.i.d. regimen (45/6.4 mg/kg/day q12h) with a 10-day amoxicillin and clavulanate potassium t.i.d. regimen (40/10 mg/kg/day q8h) in 575 patients with acute otitis media, aged 2 months to 12 years. The incidence of diarrhea was significantly lower in patients who received the b.i.d. regimen compared to patients who received the t.i.d. regimen (9.6% vs. 26.7%; p<0.001).
Significantly fewer patients who received the b.i.d. regimen withdrew due to diarrhea compared to patients receiving the t.i.d. regimen (2.8% vs. 7.6%; p=0.009). The incidence of related/possibly related diaper rash was also lower in patients who received the b.i.d. regimen compared to patients who received the t.i.d. regimen (3.1% vs. 6.6%; p =0.054).
8.5 Post-Market Adverse Reactions
The following adverse reactions have been observed during therapy with amoxicillin and clavulanate potassium:
Black hairy tongue has been reported very rarely. Tooth discolouration has been reported very rarely in children and adults. Good oral hygiene may help to prevent tooth discolouration as it can often be removed by brushing.
Central Nervous System Effects
Aseptic meningitis.
Convulsions may occur with impaired renal function or in those receiving high doses.
Gastrointestinal
Diarrhea has been reported very commonly in adults and commonly in children. Nausea and vomiting have been reported commonly in adults and children. Mucocutaneous candidiasis has been reported commonly. Abdominal cramps, flatulence, constipation, anorexia, colic pain, acid stomach, intestinal candidiasis, antibiotic-associated colitis (including pseudomembranous colitis and haemorrhagic colitis), have been reported rarely. Drug-induced enterocolitis syndrome has been reported (see 7 WARNINGS and PRECAUTIONS, Hypersensitivity Reactions). Indigestion has been reported as an uncommon occurrence. If gastrointestinal reactions are evident, they may be reduced by taking M-AMOXI CLAV at the start of the meal.
Hemic and Lymphatic Systems
As with other β-lactams, anemia, hemolytic anemia thrombocytopenia, thrombocytopenic purpura, eosinophilia, leukopenia, lymphocytopenia, basophilia, slight increase in platelets, neutropenia and agranulocytosis have been reported rarely during therapy with the penicillins. These reactions are usually reversible on discontinuation of therapy and are believed to be hypersensitivity phenomena. Prolongation of bleeding time and prolongation of prothrombin time have also been reported.
Immune
Note: If any hypersensitivity dermatitis reaction occurs, treatment with M-AMOXI CLAV should be discontinued (see 7 WARNINGS and PRECAUTIONS, Hypersensitivity Reactions).
General hypersensitivity reactions: Erythematous maculopapular rash, urticaria, anaphylaxis (see 7 WARNINGS and PRECAUTIONS, Hypersensitivity Reactions), hypersensitivity vasculitis and pruritus.
Skin and subcutaneous tissue disorders
Severe cutaneous adverse reactions (SCAR): Rarely erythema multiforme and Stevens-Johnson syndrome (SJS) have been reported. Other reactions including angioedema, toxic epidermal necrolysis (TEN), bullous exfoliative dermatitis, and acute generalised exanthematous pustulosis (AGEP) as in the case of other β-lactam antibiotics, have been seen rarely. Drug reaction with eosinophilia and systemic symptoms (DRESS) has also been reported.
Symmetrical drug-related intertriginous and flexural exanthema (SDRIFE) has been reported.
Linear IgA disease has also been reported.
Other immune system disorders: A morbilliform rash in patients with mononucleosis. Interstitial nephritis can occur rarely, Kounis syndrome (7 WARNINGS AND PRECAUTIONS, Hypersensitivity Reactions), Serum sickness-like syndrome.
Liver
Transient hepatitis and cholestatic jaundice have been reported rarely. These events have been noted with other penicillins and cephalosporins. Moderate rises in AST (SGOT), alkaline phosphatase, lactic dehydrogenase, and/or ALT (SGPT) have been noted in patients treated with ampicillin class antibiotics. The significance of these findings is unknown.
Other
Vaginitis, headache, bad taste, dizziness, malaise, glossitis, and stomatitis.
Renal and Urinary Tract Disorders
Very rare: crystalluria and interstitial nephritis (see 5 OVERDOSAGE).
9 DRUG INTERACTIONS
9.4 Drug-Drug Interactions
In common with other broad spectrum antibiotics, amoxicillin-clavulanate may reduce the efficacy of combined oral contraceptives by altering the gut-flora to result in lower estrogen reabsorption. Concomitant use of probenecid is not recommended, and may result in increased and prolonged blood levels of amoxicillin, but not of clavulanic acid.
Increases in prothrombin time, INR or bleeding have been reported in patients maintained on coumarin anticoagulants, such as acenocoumarol and warfarin and then coadministered amoxicillin or amoxicillin and clavulanate potassium. If coadministration is necessary, the prothrombin time or INR should be carefully monitored upon antibiotic addition or withdrawal.
Reduction in the median pre-dose concentration of the mycophenolic acid (MPA), the active metabolite of mycophenolate mofetil, of approximately 54% has been reported in renal transplant recipients in the days immediately following the commencement of oral amoxicillin-clavulanic acid.
These reductions in pre-dose MPA concentrations from baseline (mycophenolate mofetil alone) tended to diminish with continued antibiotic use and cease after discontinuation. The change in pre-dose level may not accurately represent changes in overall MPA exposure; therefore, clinical relevance of these observations is unclear.
Penicillins may reduce the excretion of methotrexate causing a potential increase in toxicity.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
M-AMOXI CLAV may:
- cause false-positive reactions when testing for the presence of glucose in urine.
- distort assay results for estriol in pregnant women.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Amoxicillin exerts a bactericidal action against sensitive organisms during the stage of active multiplication through the inhibition of the biosynthesis of bacterial cell wall mucopeptides. Clavulanic acid inhibits specific β-lactamases of some microorganisms and allows amoxicillin to inhibit amoxicillin (ampicillin) resistant organisms which produce clavulanic acid sensitive β-lactamases.
10.3 Pharmacokinetics
There is no significant difference between the absorptions of amoxicillin and clavulanic acid, whether administered separately or as a combination in amoxicillin and clavulanate potassium.
The half-life of amoxicillin when given alone is 1.2 hours and 1.3 hours when given in the form of amoxicillin and clavulanate potassium. The half-life of clavulanic acid alone is 1.0 hour. Time above the minimum inhibitory concentration of 1.0 mcg/mL for amoxicillin has been shown to be similar after corresponding b.i.d. and t.i.d. dosing regimens of amoxicillin and clavulanate potassium in adults and children.
Concurrent administration of probenecid delays amoxicillin excretion but does not delay renal excretion of clavulanic acid.
Neither component of M-AMOXI CLAV is highly protein-bound; clavulanic acid has been found to be approximately 30% bound to human serum protein and amoxicillin approximately 20% bound.
Special Populations and Conditions
Pediatrics
The plasma concentrations of amoxicillin and clavulanic acid following single doses of an oral suspension containing amoxicillin and clavulanic acid in a ratio of 4:1 are given in Table 4 below.
Table 4 Mean Plasma Concentrations of Amoxicillin and Clavulanic Acid
| No. of | Mean Age | Drug | Dose* | Mean Plasma Concentrations (mg/mL) at Indicated Time (h) After Dosing | |||||
|---|---|---|---|---|---|---|---|---|---|
| Children | (Years) | (mg/kg) | 1/3 | 2/3 | 1 | 2 | 3 | 4 | |
| 17 | 3.5 | amoxicillin | 6.6 | 0.91 | 1.58 | 2.11 | 2.16 | 1.23 | 0.71 |
| clavulanic acid | 1.7 | 0.29 | 0.72 | 0.67 | 0.47 | 0.20 | 0.04 | ||
| 17 | 4.1 | amoxicillin | 13.3 | 1.80 | 3.56 | 4.67 | 3.31 | 1.95 | 1.14 |
| clavulanic acid | 3.3 | 0.42 | 1.12 | 1.45 | 1.02 | 0.52 | 0.25 | ||
*A single dose of 6.6 mg/kg of amoxicillin plus 1.7 mg/kg of clavulanic acid is equivalent to one third of the daily dose of 25 mg/kg of amoxicillin and clavulanate potassium oral suspension (4:1 ratio). A single dose of 13.3 mg/kg of amoxicillin plus 3.3 mg/kg of clavulanic acid is equivalent to one third of the daily dose of 50 mg/kg of amoxicillin and clavulanate potassium oral suspension (4:1 ratio).
Some pharmacokinetic parameters for these children are given in Table 5 below.
Table 5 Pharmacokinetic Parameters
| No. of Children | Drug | Dose (mg/kg) | Plasma Half-life (h) | AUC (mg/mL-h) | Volume of Distribution (mL/kg) | Volume of Distribution (mL/min/1.73m2) |
|---|---|---|---|---|---|---|
| 17 | amoxicillin | 6.6 | 1.25 | 6.11 | 1950 | 504 |
| clavulanic acid | 1.7 | 1.10 | 1.66 | 1622 | 478 | |
| 17 | amoxicillin | 13.3 | 1.46 | 12.90 | 2172 | 481 |
| clavulanic acid | 3.3 | 1.17 | 3.54 | 1575 | 435 |
The steady state pharmacokinetic profiles of amoxicillin and clavulanic acid were compared after dosing amoxicillin and clavulanate potassium oral suspension at a dose of 45/6.4 mg/kg/day (7:1 ratio) q12h and 40/10 mg/kg/day (4:1 ratio) q8h in pediatric patients with age ranges from 1 month to 12 years. The elimination kinetics of amoxicillin and clavulanic acid in b.i.d. or t.i.d. regimens to pediatric patients aged 4 months or greater were similar to those of adults. However, in infants younger than 4 months, half-lives were delayed due to the relative immaturity of renal function in these infants.
11 STORAGE, STABILITY AND DISPOSAL
Powder: Store in the original carton to protect from light and moisture at room temperature (15°C – 30°C). Use the powder only if its appearance is white to off-white.
The reconstituted M-AMOXI CLAV (250 mg / 62.5 mg per 5 mL) oral suspension should be stored under refrigeration (2°C to 8°C) and should be used within 10 days. Discard unused suspension after 10 days.
The reconstituted M-AMOXI CLAV (400 mg / 57 mg per 5 mL) oral suspension should be stored under refrigeration (2°C to 8°C) and should be used within 7 days. Discard unused suspension after 7 days.
Keep bottle tightly closed at all times.
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
There are no special handling instructions.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
| Drug Substance | |
|---|---|
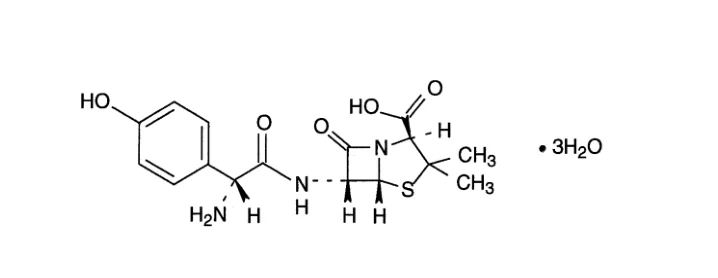
| Amoxicillin | |
| Proper Name: | Amoxicillin Trihydrate |
| Chemical Name: | (2S,5R,6R)-6-[[(2R)-2-amino-2-(4-hydroxyphenyl)acetyl]amino]-3,3-dimethyl-7-oxo-4-thia-1-azabicyclo[3.2.0]heptane-2-carboxylic acid trihydrate |
| Molecular formula and molecular mass: | C16H19N3O5S.3H20 419.47 g/mol (trihydrate) 365.41 g/mol (anhydrous) |
| Structural Formula: | |
| Physicochemical properties: | Amoxicillin trihydrate is a white or almost white highly hydroscopic crystalline powder. Amoxicillin trihydrate is slightly soluble in water, very slightly soluble in ethanol (96 per cent), practically insoluble in fatty oils. It dissolves in dilute acids and dilute solutions of alkali hydroxides. |
| Clavulanate Potassium | |
|---|---|
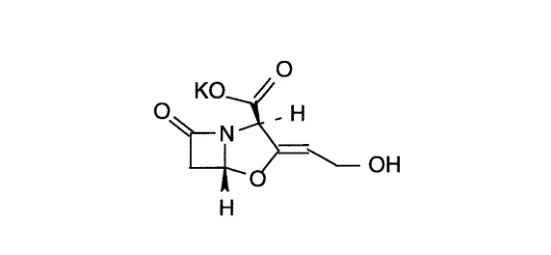
| Proper Name: | Clavulanate Potassium |
| Chemical Name | Potassium (Z)-(2R,5R)-3-(2-hydroxyethylidene)-7- oxo-4-oxa-1-azabicyclo[3,2,0]-heptane-2-carboxylate |
| Molecular formula and molecular mass: | C8H8NO5K |
 |
199.16 g/mol (free acid) 237.25 g/mol (potassium salt) | |
| Structural Formula: | |
| Physicochemical properties: | A white or almost white powder. Clavulanante Potassium is freely soluble in water, slightly soluble in ethanol (96 per cent) and very slightly soluble in acetone. |
14 CLINICAL TRIALS
Clinical Trial information was not included in Product Monograph at the time of initial authorization.
14.2 Comparative Bioavailability Studies
A double blind, randomized, two-treatment, two-period, two-sequence, cross-over, single-dose oral comparative bioequivalence study of M-AMOXI CLAV 400 mg and 57 mg /5 mL powder for oral suspension (Mantra Pharma Inc.) and PrCLAVULIN-400 powder for oral suspension (GlaxoSmithKline Inc.) was conducted in 36 healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 33 subjects that were included in the statistical analysis are presented in the following table:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Amoxicillin (5 mL × 400 mg amoxicillin/57 mg clavulanate potassium per 5 mL) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (ng·h/mL) | 24134.76 24601.45 (19.85) | 23918.43 24376.25 (20.47) | 100.9 | 98.5 – 103.4 |
| AUCI (ng·h/mL) | 24449.07 24914.62 (19.69) | 24248.10 24699.05 (20.21) | 100.8 | 98.5 – 103.2 |
Cmax (ng/mL) | 7539.47 7782.98 (25.40) | 7704.11 7962.79 (26.87) | 97.9 | 93.8 – 102.0 |
 |
Amoxicillin (5 mL × 400 mg amoxicillin/57 mg clavulanate potassium per 5 mL) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
Tmax3 (h) | 1.75 (0.75 - 3.00) | 1.75 (0.75 - 2.50) | ||
T½4 (h) | 1.42 (16.22) | 1.40 (14.14) | ||
1 M-AMOXI CLAV (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 400 mg/57 mg per 5 mL (Mantra Pharma Inc.)
2 PrClavulin-400 (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 400 mg/57 mg per 5 mL (GlaxoSmithKline Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clavulanic acid (5 mL × 400 mg amoxicillin/57 mg clavulanate potassium per 5 mL) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90 % Confidence Interval |
| AUCT (ng·h/mL) | 4063.06 4386.21 (33.61) | 3854.98 4190.57 (37.94) | 105.4 | 95.4 – 116.4 |
| AUCI (ng·h/mL) | 4136.59 4455.46 (33.15) | 3931.91 4261.46 (37.39) | 105.2 | 95.6 – 115.8 |
Cmax (ng/mL) | 1613.55 1726.74 (32.29) | 1590.19 1692.52 (34.49) | 101.5 | 92.4 – 111.5 |
Tmax3 (h) | 1.75 (0.75 - 3.00) | 1.75 (0.75 - 2.50) | ||
T½4 (h) | 1.42 (16.22) | 1.40 (14.14) | ||
1 M-AMOXI CLAV (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 400 mg/57 mg per 5 mL (Mantra Pharma Inc.)
2 PrClavulin-400 (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 400 mg/57 mg per 5 mL (GlaxoSmithKline Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
A randomized, two-way, single-dose, crossover comparative bioavailability study of M-AMOXI CLAV 250 mg/62.5 mg per 5 mL powder for oral suspension (Mantra Pharma Inc.) and PrCLAVULIN-250F powder for oral suspension (GlaxoSmithKline Inc.) was conducted in healthy, adult, male subjects under fasting conditions. Comparative bioavailability data for amoxicillin and clavulanic acid from 43 and 42 subjects, respectively, are presented in the following tables.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Amoxicillin (5 mL × 250 mg amoxicillin/62.5 mg clavulanate potassium per 5 mL) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng∙hr/mL) | 13972.13 14439.80 (26.82) | 14722.38 15184.16 (25.55) | 94.9 | 91.4 – 98.5 |
AUCI (ng∙hr/mL) | 14286.76 14746.16 (26.22) | 15042.81 15492.55 (24.93) | 95.0 | 91.6 – 98.5 |
Cmax (ng/mL) | 5533.48 5818.02 (31.77) | 6131.53 6419.74 (30.45) | 90.2 | 83.7 – 97.3 |
| Tmax3 (hr) | 1.25 (0.50 – 3.00) | 1.25 (0.50 – 2.25) | ||
| T1/24 (hr) | 1.16 (29.83) | 1.16 (16.19) | ||
1 M-AMOXI CLAV (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 250 mg/62.5 mg per 5 mL (Mantra Pharma Inc.)
2 PrCLAVULIN-250F (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 250 mg/62.5 mg per 5 mL (GlaxoSmithKline Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Clavulanic Acid (5 mL × 250 mg amoxicillin/62.5 mg clavulanate potassium per 5 mL) Uncorrected for Potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng∙hr/mL) | 3483.76 3759.92 (37.64) | 3853.85 4072.70 (29.91) | 90.4 | 81.7 – 100.0 |
AUCI (ng∙hr/mL) | 3546.14 3819.11 (37.18) | 3919.09 4138.98 (29.71) | 90.5 | 81.8 – 100.1 |
Cmax (ng/mL) | 1745.48 1871.92 (35.16) | 1895.62 1992.25 (29.93) | 92.1 | 82.9 – 102.3 |
Clavulanic Acid (5 mL × 250 mg amoxicillin/62.5 mg clavulanate potassium per 5 mL) Uncorrected for Potency Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
| Tmax3 (hr) | 1.00 (0.50 – 2.00) | 1.00 (0.25 – 4.00) | ||
| T1/24 (hr) | 1.00 (27.91) | 1.04 (19.88) | ||
Corrected for Potency Geometric Mean | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng∙hr/mL) | 3336.94 | 3333.78 | 100.1 | 90.4 – 110.8 |
AUCI (ng∙hr/mL) | 3396.69 | 3390.22 | 100.2 | 90.6 – 110.8 |
Cmax (ng/mL) | 1671.91 | 1639.81 | 102.0 | 91.8 – 113.3 |
1 M-AMOXI CLAV (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 250 mg/62.5 mg per 5 mL (Mantra Pharma Inc.)
2 PrCLAVULIN-250F (amoxicillin as amoxicillin trihydrate and clavulanic acid as clavulanate potassium) powder for oral suspension, 250 mg/62.5 mg per 5 mL (GlaxoSmithKline Inc.)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV%) only
15 MICROBIOLOGY
In the list below, organisms are categorised according to their in vitro susceptibility to amoxicillin-clavulanate based mainly on studies published during 2001-2011.
Table 6 In vitro susceptibility of micro-organisms to amoxicillin-clavulanate
Where clinical efficacy of amoxicillin-clavulanate has been demonstrated in clinical trials this is indicated with an asterisk (*). Organisms that do not produce beta-lactamase are identified (with †). If an isolate is susceptible to amoxicillin, it can be considered susceptible to amoxicillin-clavulanate. |
|---|
| Commonly susceptible species |
Gram-positive aerobes: Enterococcus faecalis Streptococcus bovis Streptococcus pyogenes† Streptococcus agalactiae† Streptococcus spp. (other β-hemolytic) † Staphylococcus aureus (methicillin susceptible)* Staphylococcus saprophyticus (methicillin susceptible) Coagulase negative staphylococcus (methicillin susceptible) |
|---|
Gram-negative aerobes: Haemophilus influenzae* Haemophilus parainfluenzae Moraxella catarrhalis* Pasteurella multocida Proteus mirabilis |
Gram positive anaerobes: Clostridium spp. Peptostreptococcus spp. |
Gram-negative anaerobes: Eikenella corrodens Fusobacterium spp. Porphyromonas spp. Prevotella spp. |
| Species for which acquired resistance may be a problem |
Gram-positive aerobes: Streptococcus pneumoniae† Viridans group streptococcus |
Gram-negative aerobes: Escherichia coli* Klebsiella oxytoca Klebsiella pneumoniae* Klebsiella spp. Proteus vulgaris Salmonella spp. Shigella spp. |
Gram-negative anaerobes: Bacteroides fragilis Bacteroides spp. Bacteroides thetiotamicron |
|---|
| Inherently resistant organisms |
Gram-positive aerobes: Enterococcus faecium |
Gram-negative aerobes: Acinetobacter spp. Aeromonas spp. Citrobacter spp. Enterobacter spp. Hafnia alvei Morganella morganii Providencia rettgeri Providencia stuartii Pseudomonas spp. Serratia marcescens |
Susceptibility Testing
Interpretive Criteria for Dilution and Disk Diffusion Testing
MIC and disk diffusion results should be interpreted according to Table 7 and are based on CLSI methodologies (CLSI M7-A910 and M2-A1011). The recommended dilution pattern utilizes a constant amoxicillin/clavulanate potassium ratio of 2 to 1 in all tubes with varying amounts of amoxicillin. MICs are expressed in terms of the amoxicillin concentration in the presence of clavulanic acid at a constant 2 parts amoxicillin to 1 part clavulanic acid. The disk procedure uses paper disks impregnated with 30 mcg amoxicillin/clavulanate potassium (20 mcg amoxicillin plus 10 mcg clavulanate potassium).
A report of S (“Susceptible”) indicates that the antimicrobial is likely to inhibit growth of the pathogen if the antimicrobial compound in the blood reaches the concentration usually achievable. A report of I (“Intermediate”) indicates that the result should be considered equivocal, and, if the microorganism is not fully susceptible to alternative, clinically feasible antimicrobials, the test should be repeated. This category implies possible clinical applicability in body sites where the drug is physiologically concentrated or in situations where high doses of antimicrobial can be used. This category also provides a buffer zone that prevents small uncontrolled technical factors from causing major discrepancies in interpretation. A report of R (“Resistant”) indicates that the antimicrobial is not likely to inhibit growth of the pathogen if the antimicrobial compound in the blood reaches the concentration usually achievable; other therapy should be selected.
Table 7 Susceptibility Test Result Interpretive Criteria for Amoxicillin/Clavulanate Potassium
| Pathogen | Minimum Inhibitory Concentration (mcg/mL) | Disk Diffusion (Zone Diameter in mm) | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| S | I | R | S | I | R | ||||||||||||
Haemophilus influenzae (Note 1) | ≤ 4/2 | Not applicable (NA) | ≥ 8/4 | ≥ 20 | NA | ≤ 19 | |||||||||||
| Enterobacteriaceae | ≤ 8/4 | 16/8 | ≥ 32/16 | ≥ 18 | 14 to 17 | ≤ 13 | |||||||||||
Staphylococcus aureus (Note 2) | ≤ 4/2 | NA | ≥ 8/4 | ≥ 20 | NA | ≤ 19 | |||||||||||
Streptococcus pneumoniae (nonmeningitis isolates) | ≤ 2/1 | 4/2 | ≥ 8/4 | (Note 3) | |||||||||||||
Note 1: β-lactamase–negative, ampicillin-resistant H. influenzae isolates must be considered resistant to amoxicillin/clavulanate potassium
Note 2: Staphylococci which are susceptible to amoxicillin/clavulanate potassium but resistant to methicillin or oxacillin must be considered as resistant
Note 3: Susceptibility of S. pneumoniae should be determined using a 1-mcg oxacillin disk. Isolates with oxacillin zone sizes of ≥ 20 mm are susceptible to amoxicillin/clavulanate potassium. An amoxicillin/clavulanate potassium MIC should be determined on isolates of S. pneumoniae with oxacillin zone sizes of ≤ 19 mm.
Quality Control Reference Ranges
Standardized susceptibility test procedures require the use of quality control microorganisms to determine the performance of the test procedures. The expected quality control results based on CLSI MIC and disk diffusion methods are shown in Table 8 (CLSI M100-S21).
Table 8 Acceptable Quality Control Ranges for Amoxicillin/Clavulanate Potassium
| Quality Control Organism | Minimum Inhibitory Concentration Range (mcg/mL) | Disk Diffusion (Zone Diameter Range in mm) |
|---|---|---|
Escherichia coli ATCC 35218 [H. influenzae quality control (Note 1)] | 4/2 to 16/8 | 17 to 22 |
| Escherichia coli ATCC 25922 | 2/1 to 8/4 | 18 to 24 |
| Haemophilus influenzae ATCC 49247 | 2/1 to 16/8 | 15 to 23 |
| Staphylococcus aureus ATCC 29213 | 0.12/0.06 to 0.5/0.25 | Not applicable (NA) |
| Staphylococcus aureus ATCC 25923 | NA | 28 to 36 |
| Streptococcus pneumoniae ATCC 49619 | 0.03/0.015 to 0.12/0.06 | NA |
ATCC is a trademark of the American Type Culture Collection.
Note 1: When using Haemophilus Test Medium (HTM)
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Single Dose
The acute toxicity of amoxicillin trihydrate and potassium clavulanate, formulated in a 2:1 and 4:1 ratio, was determined in mice and rats dosed orally and intravenously. LD50's are shown in Table 9.
Table 9 Acute Toxicity
| Species | Route | Sex | Drug Ratio | LD50 (mg/kg)** | ||||||
|---|---|---|---|---|---|---|---|---|---|---|
| Rats | Oral | M | 2:1 | >5000 | ||||||
| F | 2:1 | >5000 | ||||||||
| Mice | Oral | M | 2:1 | >5000 | ||||||
| F | 2:1 | >5000 | ||||||||
| Rats | Oral | M | 4:1 | >5000 | ||||||
| F | 4:1 | >5000 | ||||||||
| i.v. | M | 4:1 | 1850 | |||||||
| F | 4:1 | 1960 | ||||||||
| Mice | Oral | M | 4:1 | >5000 | ||||||
| F | 4:1 | >5000 | ||||||||
| i.v | M | 4:1 | 1715-2450* | |||||||
| F | 4:1 | 1715-2450* | ||||||||
* estimated
** calculated in terms of amoxicillin and clavulanic acid.
All animals were observed for 14 days. Soft faeces which were observed in rats at the beginning of the observation period regained good general condition by the end of the observation period. All mice showed a slight dose-related loss of condition for up to 72 hours after dosing, thereafter remaining in good condition for the duration of the study. Animals, dosed by the intravenous route, which survived were observed to have mild convulsions and abnormal gait 2-3 minutes after dosing. Those, which did not survive, convulsed immediately on dosing and died within 1 minute.
The LD50 of clavulanate potassium administered orally to 4 day old rats was determined to be 1,360 mg/kg. This compares with an oral LD50 of greater than 10,000 mg/kg for adult rats. In these neonates, weight loss, diarrhea and abdominal distension were frequently observed following dosing.
Repeat Dose
Rats
Amoxicillin trihydrate and clavulanate potassium formulated in a 2:1 ratio were administered orally by gavage to 3 groups of rats each comprising 10 males and 10 females at doses of 20/10,
60/30 or 180/90 mg/kg/day for 4 weeks. A fourth group served as a control. Clinical condition and laboratory determinations were monitored and post-mortem and histopathologic determinations were carried out. There were no deaths during the study. Apart from the passage of slightly soft faeces in all treated groups, there were no adverse clinical signs. Body weight gain and food intake were comparable with controls. Water intake was increased in the male high dose group (8%, 16.3%, 16.8% and 12.2% for weeks 1, 2, 3 and 4, respectively). Female rats showed an overall increase in water consumption of 22%, 11% and 13% for low, intermediate and high dose groups, respectively. Hematology and blood chemistry parameters were comparable to controls and within accepted normal limits. There was a statistically significant increase in urine output in the low and high dose male groups compared to controls. Macroscopic examination revealed an increased incidence of caecal enlargement in all treated groups and was marginally greatest at the high dose level. There was a statistically significant decrease in relative liver weights in both sexes (-9%, -14% and -9% for high, intermediate and low dose male groups, respectively and -12%, -16% and -6% for equivalent female groups). The mean relative thymus weight in the high dose male group was also significantly decreased by 21% and the relative heart weight in the intermediate dose female group was significantly reduced by 12% compared with control. Histological examination of the kidneys revealed minimal chronic inflammatory cell infiltration in a proportion of animals from all groups and was associated with occasional distended tubules and tubules characterized by basophilic staining of the cells of the epithelium.
Amoxicillin trihydrate and clavulanate potassium formulated in a 2:1 ratio were administered orally by gavage to four groups of Sprague-Dawley rats, each comprising 15 males and 15 females, at doses of 20/10, 40/20, 100/50 or 800/400 mg/kg/day for 26 weeks. A fifth group served as a control. Five male and 5 female rats were added to each of the high dose and control groups to determine the effect of drug withdrawal. At the end of the treatment period, these two groups were left undosed for a period of four weeks before sacrificing. Clinical condition and laboratory determinations were monitored and post-mortem and histopathologic determinations were carried out.
There were 4 deaths during the treatment period: one male and two females in the 20/10 mg/kg/day group and one female in the 40/20 mg/kg/day group. There were no deaths during the withdrawal period. Salivation immediately after dosing was noted in both male and female high dose groups. For males receiving 800/400 mg/kg/day, 21% lower body weight gains were recorded from week 3 onwards and 10% lower body weight gains were recorded in the 100/50 mg/kg/day group. Females receiving 800/400 mg/kg/day had lower body weight gains of 62% recorded from week 13.
Decreased urine volumes (males - 30%, females - 54%) were recorded in the 800/400 mg/kg/day group. A statistically significant increase in osmolality was noted in the female high dose group compared to controls.
There was an increase in total white blood cell count associated with an increase in lymphocytes in male rats from the high dose group. This group also had shorter APTT (Activated Partial Thromboplastin Time) while a non-dose related shortened PT (Prothrombin Time) was observed for males receiving 800/400, 100/50, or 40/20 mg/kg at various intervals during treatment, and for all treated males after 24 weeks. At the end of the withdrawal period, values for all parameters were similar to controls. Blood chemistry investigations revealed lower serum albumin (5 to 16%) and higher globulin levels (16 to 30%) during weeks 12 and 24 for male animals receiving 800/400 mg/kg, with an associated decrease in A/G ratios.
A similar effect was seen at week 24 for males receiving 100/50 mg/kg. High dose female rats had globulin levels and A/G ratios similar to controls. However, total protein levels were lower than controls, with an associated decrease in serum albumin levels. At the end of the withdrawal period the only difference from controls was a reduction in total serum protein in females.
At post-mortem examination, a prominent limiting ridge was seen in the stomachs of nearly all the high dose group rats and 1 male dosed at 100/50 mg/kg. Distension of the caecum was seen at all dose levels in a dose-related fashion. At the end of the withdrawal period these findings were no longer observed. Significantly increased liver weights (males - 40%; females - 22%), spleen weights (females - 23%) and kidney weights (males - 10%) were recorded for the high dose group. There was an increase of 30% in liver weights in high dose females and an increase of 26% in kidney weights of high dose males at the end of the withdrawal period. Treatment related microscopic effects were seen in high dose rats of both sexes.
These were hepatocyte enlargement in centrilobular and mid-zonal areas of the liver, hyperplasia of the non-glandular epithelium of the stomach in the region of the limiting ridge and distension of the lumen of the caecum. The only persistent change present after the withdrawal period was hepatocyte enlargement in all previously dosed males.
A study of similar design was carried out in which identical doses of only the clavulanic acid component of the combination described above were administered. In general, the results were similar to those reported above for the combination.
Dogs
Amoxicillin trihydrate and clavulanate potassium formulated in a 2:1 ratio were administered orally by gavage to 3 groups of beagle dogs, each comprising 2 males and 2 females, at doses of 20/10, 60/30 or 180/90 mg/kg/day for 28 days. A fourth group served as a control. Clinical condition and laboratory determinations were monitored and post-mortem and histopathologic determinations were carried out. There were no deaths during the study. The high dose animals showed immediate signs of excessive salivation and severe vomiting was seen up to 2-1/2 hours after dosing. Vomiting was present but less severe in the female intermediate dose group. Body weight gain, food and water consumption and hematology were unaffected by treatment. The blood glucose level of the 60/30 mg/kg dosed male dogs was raised 25% on day 13 and 11% on day 27. These two dogs also showed increases in mean BUN (70%), total protein (5%) and albumin (10%) concentrations at the terminal bleed. The high dose group had reduced total protein (11%) and albumin (10%) levels on day 27. Female dogs dosed at 180/90 mg/kg had total protein levels reduced by 4% and total albumin levels reduced by 12% and 10% at interim and terminal bleeds.
All dose groups had SGOT activity slightly reduced on days 13 and 27. A pronounced enzymuria and minor proteinuria was seen in one male dog of the low dose group. All dosed groups had slight elevation in osmolality and electrolyte excretion. The low dose female group had a slight elevation in urinary alkaline phosphatase (UAP) activity while the urine concentration capacity of test animals was marginally raised. Macroscopic post-mortem examinations did not reveal any treatment-related changes. Histological examination revealed that in the colon of two female dogs in the high dose group, distended glands were prominent and were associated with chronic inflammatory changes both in the colon and in the mucosa of the duodenum in one instance. No other changes were observed that would be considered to be related to the administration of the test compound.
Amoxicillin trihydrate and clavulanate potassium formulated in a 2:1 ratio were administered orally by gavage to four groups of Beagle dogs, each comprising 4 females and 4 males, at doses of 10/5, 20/10, 40/20 or 100/50 mg/kg/day for 26 weeks. A fifth group served as a control. Three male and 3 female dogs were added to each of the high dose and control groups to determine the effect of drug withdrawal. At the end of the treatment period, these two groups were left undosed for a period of 30 days before sacrificing. Clinical condition and laboratory determinations were monitored and post-mortem and histopathologic determinations were carried out.
There were no deaths during the study. Salivation and emesis including the occasional presence of blood streaks (1 mL) in the vomitus were observed in the high dose groups. A low incidence of fecal occult blood was observed in both treated and control animals but the highest incidence occurred in the high dose group after 3 months of treatment. Abnormal granulations in segmented neutrophils were observed most frequently in animals from the high dose group.
Serum glucose levels in males from all treated groups and females from the low and high dose groups were found to be 8 - 29% greater than in controls on some of the assessment occasions during treatment. Similarly, high dose males and females had decreased total protein levels of 9 - 13% on various occasions during treatment. In both cases the absolute magnitude of the change was small with the observed values not falling outside of normal ranges for Beagle dogs. Focal reddening and petechiation of the mucosa of the pyloric antrum, the presence of white patchy areas in the liver and the presence of white streaks along the cortico-medullary junctions of the kidneys were recorded more frequently for animals of the treated groups than for control animals. At the end of the recovery period kidney changes and some GI effects remained. Histopathological studies revealed hepatic and renal changes in the form of cytoplasmic glycogen diminution or disappearance and tubular vacuolization. The kidney and liver changes identified in dogs killed after 6 months of treatment were not observed in dogs of the regression group. Histopathological examination of the GI tract revealed capillary congestion and some extravasation of erythrocytes in the superficial mucosa of the fundus and pylorus in both treated and control dogs.
A study of similar design was carried out in which identical doses of only the clavulanic acid component of the combination described above were administered. In general, the results were similar to those reported above for the combination.
Reproductive and Developmental Toxicology
Fertility and General Reproductive Performance
Amoxicillin trihydrate and clavulanate potassium in a 2:1 ratio were administered orally by gavage to 3 groups of rats, each comprising 24 males and 24 females, at doses of 20/10, 100/50 or 800/400 mg/kg/day. A fourth group served as a control. Male rats were dosed daily for a minimum of 63 days prior to mating and continuing until weaning of offspring on day 21. Female rats were treated for 15 days prior to mating until weaning or until selected for caesarean section at the end of gestation. On gestation day 20, 10 females/group were sacrificed, a caesarean section was carried out and the remaining 14 females/group were allowed to litter normally. Two high dose males died, one each during study week 11 and 15. Necropsy indicated impaction of the caecal content for one while the other showed pulmonary hemorrhage. Treatment related effects in the high dose males included a slight increase in wheezing and hair loss, decrease in mean body weight gain (21%) and a moderate increase in soft stools.
A slight increase in hair loss was noted in the 100/50 and 800/400 mg/kg/day females. Fertility and general reproductive performance was not affected by treatment as assessed by pregnancy rate and duration of gestation. Male and female mean pup body weights were statistically significantly higher in the 100/50 mg/kg/day group when compared to control. Although not statistically significant, a decrease, which tended to be dose related, was observed with respect to viable fetuses, total implantations and corpora lutea per dam. Two F1 fetuses, from the 800/400 mg/kg dose group, had malformations (one had a malformed scapula and the other a thread-like tail and small anus). Litter size, foetal loss and development and behaviour of pups were not adversely affected by treatment.
A study of similar design was carried out in which identical doses of only the clavulanic acid component of the combination described above were administered. The results were generally similar to those reported above for the combination with the addition that 2 fetuses from the 400 mg/kg/day dose group exhibited scoliosis.
Teratology
Three groups of 30 female rats were mated and amoxicillin trihydrate and clavulanate potassium in a 2:1 ratio were then administered from day 6 to day 15 of gestation at doses of 20/10, 100/50 or 800/400 mg/kg/day. A fourth group served as a control. On day 20 of gestation, 20 females/group were sacrificed and a caesarean section was carried out while the remaining 10/group were allowed to litter normally. One dam in the 100/50 mg/kg/day group died; however, the dam was normal internally. Maternal observations revealed a dose related loss of hair, a reduction (11 to 23%) in mean maternal body weight gain for gestation days 6 to 20 and a decrease in food consumption. Slight increases in post-implantation losses were seen in the treated groups, but these were neither dose-related nor statistically significant. Pregnancy rate, litter size, foetal loss and mean pup weights were not affected by the treatment.
The incidence of bent ribs was dose-related and scoliosis was observed in three offspring of dams dosed at 100/50 and 800/400 mg/kg/day. Other offspring abnormalities included extra sternebrae (1 pup), numerous petechiae on the stomach and misplace sternebrae (1 pup) and cleft lip with several skeletal anomalies involving the vertebrae, ribs, skull and sternum (1 pup).
A study of similar design was carried out in which identical doses of only the clavulanic acid component of the combination described above were administered. The results were generally similar to those reported above for the combination with the addition that a dose related reduction in ossification and a statistically significant decrease in mean pup body weight were also observed.
Perinatal and Postnatal Studies
Amoxicillin trihydrate and clavulanate potassium in a ratio of 2:1 were administered orally by gavage to 3 groups, each comprising 20 pregnant rats, at doses of 20/10, 100/50 or 800/400 mg/kg/day from day 15 of gestation, through lactation to 21 days post-partum. A fourth group served as a control. Among parent animals, no deaths were observed but there was a slight decrease (17%) of mean body weight in the 800/400 mg/kg/day group on gestation days 15 to 20 and lactation days 0 to 4. Among the litters, 6 deaths were observed; 5 in the 100/50 mg/kg/day group and 1 in the 800/400 mg/kg/day group. A statistically significant decrease in mean number of viable pups per litter in the high dose group was observed. There was a statistically significant decrease in pup survival in the 100/50 mg/kg/day dose group on lactation days 4, 8, 12 and 21 and a small statistically insignificant decrease in the 800/400 mg/kg/day group. In the F1 generation animals, which were mated, a statistically significant decrease in total implantations per dam and corpora lutea was observed for animals in dams of the 800/400 mg/kg/day group compared to control. The F1 generation parameters revealed no other biologically meaningful differences or dose-related trends in litter observations, behavioural and developmental indices, neuropharmacological responses or reproductive capability of any treatment group when compared with control.
A study of similar design was carried out in which identical doses of only the clavulanic acid component of the combination described above were administered. The maternal effects observed were, in general, similar to those reported above for the combination preparation. In the F1 generation, 1 pup from each of the 50 and 400 mg/kg dosage groups had bilateral rudimentary ribs and 1 pup from the 400 mg/kg dosage group had hydrocephaly in addition to bilateral rudimentary ribs.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. CLAVULIN (tablets, oral suspension, CLAVULIN -500F, CLAVULIN -875, CLAVULIN -125F, CLAVULIN -200, CLAVULIN-250F and CLAVULIN-400), submission control 283115, Product Monograph, GlaxoSmithKline Inc. (JUN 28, 2024)