


Product Monograph - Mar-Paroxetine
RECENT MAJOR LABEL CHANGES
| Section | Date |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 06/2023 |
| 7 WARNINGS AND PRECAUTIONS, Hematologic | 08/2022 |
| 7 WARNINGS AND PRECAUTIONS, Immune | 08/2022 |
| 7 WARNINGS AND PRECAUTIONS, Neurologic | 08/2022 |
| 7 WARNINGS AND PRECAUTIONS, Psychiatric | 08/2022 |
| 7 WARNINGS AND PRECAUTIONS, Reproductive Health: Female and Male Potential | 08/2022 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | 08/2022 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ........................................................................................... 2
TABLE OF CONTENTS ............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 5
1 INDICATIONS ............................................................................................................. 5
- 1.1 Pediatrics .................................................................................................................. 5
- 1.2 Geriatrics ................................................................................................................... 5
- 2 CONTRAINDICATIONS ................................................................................................ 5
- 3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................. 6
4 DOSAGE AND ADMINISTRATION ................................................................................ 6
- 4.1 Dosing Considerations .............................................................................................. 6
- 4.2 Recommended Dose and Dosage Adjustment ......................................................... 7
- 4.4 Administration .......................................................................................................... 9
- 4.5 Missed Dose .............................................................................................................. 9
- 5 OVERDOSAGE ............................................................................................................ 9
- 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ................................ 10
7 WARNINGS AND PRECAUTIONS ................................................................................ 10
- 7.1 Special Populations ................................................................................................. 17
- 7.1.1 Pregnant Women .............................................................................................. 17
- 7.1.2 Breast-feeding ................................................................................................... 18
- 7.1.3 Pediatrics........................................................................................................... 18
- 7.1.4 Geriatrics ........................................................................................................... 18
8 ADVERSE REACTIONS ................................................................................................ 19
- 8.1 Adverse Reaction Overview .................................................................................... 19
- 8.2 Clinical Trial Adverse Reactions .............................................................................. 20
- 8.2.1 Clinical Trial Adverse Reactions – Pediatrics ..................................................... 25
- 8.3 Less Common Clinical Trial Adverse Reactions ....................................................... 26
- 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data.............................................................................................................. 28
- 8.5 Post-Market Adverse Reactions ............................................................................. 29
9 DRUG INTERACTIONS ............................................................................................... 29
- 9.1 Serious Drug Interactions ....................................................................................... 29
- 9.2 Drug Interactions Overview .................................................................................... 30
- 9.3 Drug-Behavioural Interactions ............................................................................... 30
- 9.4 Drug-Drug Interactions ........................................................................................... 30
- 9.5 Drug-Food Interactions ........................................................................................... 38
- 9.6 Drug-Herb Interactions ........................................................................................... 38
- 9.7 Drug-Laboratory Test Interactions .......................................................................... 38
10 CLINICAL PHARMACOLOGY ....................................................................................... 38
- 10.1 Mechanism of Action ........................................................................................ 38
- 10.2 Pharmacodynamics ........................................................................................... 39
- 10.3 Pharmacokinetics .............................................................................................. 39
- 11 STORAGE, STABILITY AND DISPOSAL ............................................................................ 41
- 12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 41
PART II: SCIENTIFIC INFORMATION ....................................................................................... 42
- 13 PHARMACEUTICAL INFORMATION ............................................................................ 42
14 CLINICAL TRIALS ....................................................................................................... 43
- 14.1 Clinical Trials by Indication................................................................................ 43
Major Depressive Disorder ............................................................................................... 43
Obsessive-Compulsive Disorder ....................................................................................... 43
Panic Disorder (with or without agoraphobia) ................................................................. 43
Social Phobia (Social Anxiety Disorder) ............................................................................ 44
Generalized Anxiety Disorder (GAD) ................................................................................. 44
Posttraumatic Stress Disorder (PTSD) ............................................................................... 44
14.2 Comparative Bioavailability Studies……………………………………………………………….45
- 15 MICROBIOLOGY ....................................................................................................... 45
- 16 NON-CLINICAL TOXICOLOGY ..................................................................................... 45
- 17 SUPPORTING PRODUCT MONOGRAPHS…………………………………………………………………………….47
PATIENT MEDICATION INFORMATION .................................................................................. 48
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
MAR-PAROXETINE (paroxetine hydrochloride) is indicated in adults for the symptomatic treatment of:
- Major Depressive Disorder (MDD)
- Obsessive-Compulsive Disorder (OCD)
- Panic Disorder (with or without agoraphobia)
- Social Phobia (Social Anxiety Disorder)
- Generalized Anxiety Disorder (GAD)
- Posttraumatic Stress Disorder (PTSD) Long-Term Use of Paroxetine Hydrochloride:
Clinical trials have provided evidence that continuation treatment with paroxetine hydrochloride in patients with moderate to moderately severe depressive disorder is effective for at least 6 months (see 14.1 Trial Design by indication, Major Depressive Disorder).
The effectiveness of paroxetine hydrochloride in long-term use (i.e. more than 8 weeks for GAD and 12 weeks for other indications) has not yet been established in controlled trials for OCD, panic disorder, social phobia (social anxiety disorder), generalized anxiety disorder and posttraumatic stress disorder. Therefore, the health professional who elects to use paroxetine hydrochloride for extended periods in these indications should periodically re-evaluate the long-term usefulness of the drug for individual patients (see 4.1 Dosing Considerations).
1.1 Pediatrics
Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioral and Emotional Changes, Including Self-Harm; 8.2.1 Clinical Trial Adverse Reactions – Pediatrics).
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies indicates that there are differences in the pharmacokinetic profile of paroxetine in the geriatric population relative to younger adults, which may be associated with differences in safety or effectiveness. A brief discussion can be found in the appropriate sections (see 7.1.4 Geriatrics; 10 CLINICAL PHARMACOLOGY; 4 DOSAGE AND ADMINISTRATION).
2 CONTRAINDICATIONS
MAR-PAROXETINE (paroxetine hydrochloride) is contraindicated:
- Hypersensitivity: In patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- Monoamine Oxidase Inhibitors: In combination with a monoamine oxidase inhibitor (MAOI) or within a minimum of 2 weeks of terminating or starting treatment with a MAOI (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome; 9.1 Serious Drug Interactions; 9.4 Drug-Drug Interactions).
Thioridazine: In combination with thioridazine or within a minimum of 2 weeks of terminating treatment with
- thioridazine (see 9.1 Serious Drug Interactions; 9.4 Drug-Drug Interactions).
- Pimozide: In combination with pimozide or within a minimum of 2 weeks of terminating treatment with pimozide (see 9.1 Serious Drug Interactions; 9.4 Drug-Drug Interactions).
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations General
- MAR-PAROXETINE is not indicated for use in children under the age of 18.
- Paroxetine should only be used during pregnancy if the benefits outweigh the risks, particularly during the third trimester as there are implications for neonatal health (see 4.2 Recommended Dose and Dosage Adjustment and 7.1.1 Pregnant Women).
Due to the potential for life-threatening serotonin toxicity:
- Concurrent use with MAOIs is contraindicated.
- Washout periods are necessary if switching between paroxetine and MAOIs.
- Use with other serotonergic agents is not recommended (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity /Neuroleptic Malignant Syndrome).
- Dose tapering is recommended when switching between antidepressants, including paroxetine.
Dosing:
- Reduced doses may be needed for the elderly, and those with renal impairment.
- All dose changes should be gradual, including discontinuation.
- Monitor for discontinuation symptoms when decreasing or stopping treatment.
- Periodically reassess the need for ongoing therapy.
Monitor for agitation, suicidal tendencies
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages, especially when initiating therapy or during any change in dose or dosage regimen. This includes monitoring for agitation-type emotional and behavioural changes (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
4.2 Recommended Dose and Dosage Adjustment Depression
- Usual Adult Dose: The administration of MAR-PAROXETINE should be initiated at 20 mg daily. For most patients, 20 mg daily will also be the optimum dose. The therapeutic response may be delayed until the third
Serious Warnings and Precautions
Increased risk of self-harm, harm to others, suicidal thinking and behavior with antidepressants use. Closely monitor all antidepressant-treated patients for clinical worsening and for emergence of agitation-type and/or suicidal thoughts and behaviors (see 7 WARNINGSAND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
- or fourth week of treatment.
- Dose Range: For those patients who do not respond adequately to the 20 mg daily dose, a gradual increase in dosage up to 40 mg daily may be considered. The maximum recommended daily dose is 50 mg.
Obsessive-Compulsive Disorder
Usual Adult Dose: The administration of MAR-PAROXETINE should be initiated at 20 mg/day. The recommended dose of MAR-PAROXETINE in the treatment of OCD is 40 mg daily.
- Dose Range: For those patients who do not respond adequately to the 40 mg daily dose, a gradual increase in dosage may be considered. The maximum recommended daily dose is 60 mg.
Panic Disorder
Usual Adult Dose: The recommended starting dose of MAR-PAROXETINE in the treatment of panic disorder is 10 mg/day. The recommended dose of MAR-PAROXETINE in the treatment of panic disorder is 40 mg daily.
- Dose Range: For those patients who do not respond adequately to the 40 mg daily dose, a gradual increase in dosage may be considered. The maximum recommended daily dose is 60 mg.
Social Phobia (Social Anxiety Disorder)
- Usual Adult Dose: The recommended initial dosage is 20 mg/day. No clear dose-relationship has been demonstrated over a 20 to 60 mg/day dose range.
- Dose Range: Some patients not responding adequately to a 20 mg dosage may benefit from gradual dosage increases, in 10 mg/day increments, up to a maximum of 50 mg/day.
Generalized Anxiety Disorder
- Usual Adult Dose: The recommended initial dosage is 20 mg/day.
- Dose Range: Some patients not responding adequately to a 20 mg dosage may benefit from gradual dosage increases, in 10 mg/day increments, up to a maximum of 50 mg/day.
Posttraumatic Stress Disorder
- Usual Adult Dose: The recommended starting dosage is 20 mg/day.
- Dose Range: Some patients not responding adequately to a 20 mg/day dosage may benefit from gradual dosage increases, in 10 mg/day increments, up to a maximum of 50 mg/day.
Dose Adjustments
Based on pharmacokinetic parameters, steady-state paroxetine plasma levels are achieved over a 7 to 14 day interval. Hence, dosage adjustments in 10 mg increments should be made at 1 to 2 week intervals or according to clinician judgment.
Maintenance
During long-term therapy for any indication, the dosage should be maintained at the lowest effective level.
There is no body of evidence available to answer the question of how long a patient should continue to be treated with paroxetine hydrochloride. It is generally agreed that acute episodes of depression require several months or longer of sustained pharmacologic therapy. Whether the dose of an antidepressant needed to induce remission is identical to the dose needed to maintain and/or sustain euthymia is unknown.
Systematic evaluation of the efficacy of paroxetine hydrochloride has shown that efficacy is maintained for at least 6 months with doses that averaged about 30 mg (see 14.1 Clinical Trials by Indication, Major Depressive Disorder).
Discontinuation of Treatment
Symptoms associated with the discontinuation of paroxetine hydrochloride have been reported in clinical trials and post marketing. Patients should be monitored for these and other symptoms when discontinuing treatment, regardless of the indication for which MAR-PAROXETINE is being prescribed (see 7 WARNINGS AND PRECAUTIONS, Discontinuation of treatment with MAR-PAROXETINE and 8 ADVERSE REACTIONS, Adverse Reactions following Discontinuation of Treatment (or Dose Reduction)).
A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, dose titration should be managed on the basis of the patient’s clinical response (see 8 ADVERSE REACTIONS).
Special Patient Populations
For any indication:
- Pediatrics (< 18 years): Health Canada has not authorized an indication for pediatric use. (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioral and Emotional Changes, Including Self-Harm).
- Geriatrics (> 65 years): Administration of MAR-PAROXETINE to the elderly is associated with increased plasma levels and prolongation of the elimination half-life relative to younger adults (see 10 CLINICAL PHARMACOLOGY). The recommended initial dose is 10 mg/day for elderly and/or debilitated patients. The dose may be increased, if indicated, up to a maximum of 40 mg daily.
- Renal/Hepatic Insufficiency: MAR-PAROXETINE should be used with caution in patients with renal or hepatic impairment. The recommended initial dose is 10 mg/day in patients with clinically significant renal or hepatic impairment. A maximum dose of 40 mg should not be exceeded (See 7 WARNINGS AND PRECAUTIONS and 10 CLINICAL PHARMACOLOGY).
Pregnant Women: Epidemiological studies of pregnancy outcomes following maternal exposure to antidepressants in the first trimester have reported an increase in the risk of congenital malformations, particularly cardiovascular (e.g. ventricular and atrial septal defects), associated with the use of paroxetine. If a patient becomes pregnant while taking MAR-PAROXETINE, she should be informed of the current estimate of risk to the fetus (see 7.1 Special Populations) and consideration should be given to switching to other treatment options. Treatment with MAR-PAROXETINE should only be continued for an individual patient, if the potential benefits outweigh the potential risks. For women who intend to become pregnant, or are in their first trimester of pregnancy, initiation of paroxetine should be considered only after other treatment options have been evaluated (see 7.1 Special Populations).
Post-marketing reports indicate that some neonates exposed to paroxetine hydrochloride, SSRIs, or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding (see 7.1 Special Populations). When treating pregnant women with MAR-PAROXETINE during the third trimester, the health professional should carefully consider the potential risks and benefits of treatment. The health professional may consider tapering MAR-PAROXETINE in the third trimester.
4.4 Administration
MAR-PAROXETINE should be administered once daily in the morning and may be taken with or without food. The tablet should be swallowed rather than chewed.
4.5 Missed Dose
If a dose of MAR-PAROXETINE is missed at its usual time, it should be taken as soon as possible, unless it is too close to the time of the next dose. The missed dose should be skipped if it is almost time for the next regular dose. Two doses should not be taken at the same time.
5 OVERDOSAGE
The largest known ingestion from which a patient has recovered is 2000 mg. The smallest known dose of paroxetine alone associated with a fatal outcome is approximately 400 mg.
Symptoms
The most commonly reported adverse events subsequent to paroxetine-only overdose include: somnolence, nausea, tremor, dizziness, vomiting, diarrhea, agitation, aggression, anxiety, confused state, headache, fatigue, insomnia, tachychardia, hyperhydrosis, mydriasis, convulsion, parasthesia, serotonin syndrome, fever, blood pressure changes, involuntary muscle contraction and loss of consciousness. It should be noted that in some cases, patients may have consumed alcohol in addition to taking an overdose of paroxetine. Some of these symptoms may also be seen with clinical use.
Events such as coma and ECG changes have also been reported.
Treatment
The health professional should consider contacting a poison control centre for additional information on the treatment of any overdose.
No specific antidote is known. Treatment should consist of those general measures employed in the management of overdose with any antidepressant. Establish and maintain an airway; ensure adequate oxygenation and ventilation.
Induction of emesis is not recommended. Due to the large volume of distribution of paroxetine hydrochloride, forced diuresis, dialysis, hemoperfusion and exchange transfusion are unlikely to be of benefit. Supportive care with frequent monitoring of vital signs and careful observation is indicated. An ECG should be taken and monitoring of cardiac function instituted if there is any evidence of abnormality. Patient management should be as clinically indicated, or as recommended by the national poisons centre, where available.
In managing overdosage, consider the possibility of multiple drug involvement.
A specific caution involves patients taking or recently having taken paroxetine hydrochloride who might ingest, by accident or intent, excessive quantities of a tricyclic antidepressant. In such a case, accumulation of the parent tricyclic and its active metabolite may increase the possibility of clinically significant sequelae and extend the time needed for close medical observation.
For management of a suspected drug overdose, contact your regional poison control centre.
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1– Dosage Forms, Strengths and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablet/ 10 mg, 20 mg, 30 mg | Dibasic calcium phosphate dehydrate USP, Hypromellose, Sodium Starch Glycolate, Magnesium Stearate, Titanium Dioxide, Macrogol/PEG 400, Polysorbate 80, D&C Yellow No. 10 Aluminum Lake (10 mg tablets only), FD&C Yellow No. 6/Sunset Yellow FCF Aluminum Lake (10 mg tablets only), D&C Red No. 30 Helindon Pink Aluminum Lake (20 mg tablets only), FD&C Blue No. 2-Indigo Carmine Aluminum Lake (30 mg tablets only) |
MAR-PAROXETINE is available as film coated, oval biconvex tablets containing paroxetine hydrochloride equivalent to 10 mg (yellow tablets), 20 mg (pink tablets), 30 mg (blue tablets), paroxetine free base. The tablets have “PA” engraved on one side and strength engraved on the other side. The 10 and 20 mg tablets are scored. Available in package sizes of:
10 mg - Bottles of 100
20 mg - Bottles of 100 and 500
30 mg - Bottles of 100
7 WARNINGS AND PRECAUTIONS
General
Discontinuation of treatment with MAR-PAROXETINE
Discontinuation Symptoms: Patients currently taking MAR-PAROXETINE should NOT be discontinued abruptly, due to risk of discontinuation symptoms. At the time that a medical decision is made to discontinue an SSRI or other newer antidepressant drug, a gradual reduction in the dose rather than an abrupt cessation is recommended.
When discontinuing treatment, regardless of the indication for which MAR-PAROXETINE is being prescribed, patients should be monitored for symptoms which may be associated with discontinuation (e.g. dizziness, sleep disturbances including abnormal dreams, sensory disturbances (including paresthesias, electric shock sensations and tinnitus), agitation, anxiety, headache, tremor, confusion, diarrhea, nausea, vomiting and sweating) or other symptoms which maybe of clinical significance [see 8 ADVERSE REACTIONS, Adverse Events following Discontinuation of Treatment (or Dose Reduction)]. A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, dose titration should be managed on the basis of the patient’s clinical response (see 8 ADVERSE REACTIONS and 4 DOSAGE AND ADMINISTRATION).
Potential for reduced efficacy of Tamoxifen with concomitant SSRI use, including MAR-PAROXETINE
The antitumor agent tamoxifen is a pro-drug requiring metabolic activation by CYP2D6. Inhibition of CYP2D6 can lead to reduced plasma concentrations of a primary active metabolite (endoxifen). Chronic use of CYP2D6 inhibitors, including certain SSRIs, together with tamoxifen can lead to persistent reduction in levels of endoxifen (see also 9 DRUG INTERACTIONS, Tamoxifen). Some studies have shown that the efficacy of tamoxifen, as measured by the risk of breast cancer relapse/mortality, may be reduced when co-prescribed with paroxetine hydrochloride as a result of paroxetine’s irreversible inhibition of CYP2D6. This risk may increase with longer duration of coadministration. When tamoxifen is used for the treatment of breast cancer, prescribers should consider using an alternative antidepressant with little or no CYP2D6 inhibition.
Concomitant Illnesses
Clinical experience with paroxetine hydrochloride in patients with certain concomitant systemic illnesses is limited. Caution is advisable in using MAR-PAROXETINE in patients with diseases or conditions that could affect metabolism or hemodynamic responses.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY for animal data.
Cardiovascular
Paroxetine hydrochloride has not been evaluated or used to any appreciable extent in patients with a recent history of myocardial infarction or unstable heart disease. The usual precautions should be observed in patients with cardiac conditions.
QT Prolongation
Cases of QT interval prolongation (with or without ventricular tachycardia) have been reported during post-market use of paroxetine, although causality with paroxetine hydrochloride has not been established.
MAR-PAROXETINE should be used with caution in patients with a history of QT interval prolongation, patients taking anti-arrhythmic or other medications that may potentially prolong QT interval, or those with relevant pre-existing cardiac disease (see 2 CONTRAINDICATIONS, 9.1 Serious Drug Interactions and 9.4 Drug-Drug Interactions).
Dependence/Tolerance
Paroxetine hydrochloride has not been systematically studied, in animals or humans, for its potential for abuse, tolerance, or physical dependence. Health professionals should carefully evaluate patients for history of drug abuse and follow such patients closely, observing them for signs of misuse or abuse of MAR-PAROXETINE.
Driving and Operating Machinery
Although paroxetine did not cause sedation or interfere with psychomotor performance in placebo- controlled studies in normal subjects, patients should be advised to avoid driving a car or operating hazardous machinery until they are reasonably certain that MAR-PAROXETINE does not affect them adversely.
Endocrine and Metabolism
Serum Cholesterol Elevation
Several public domain studies have shown increased LDL-cholesterol levels of ~10% in volunteers and patients taking paroxetine for 8 to 12 weeks, which generally normalized after paroxetine discontinuation. In addition, of the patients in placebo-controlled clinical trials for whom baseline and on-treatment measurements were taken, total serum levels of cholesterol showed a mean increase of ~ 1.5 mg/dL in paroxetine-treated patients(n = 653), compared to a mean decrease of ~ 5.0 mg/dL in placebo-treated patients(n = 379). Increases from baseline of 45 mg/dL or greater were recorded in 6.6% of paroxetine-treated patients compared to 2.6% of placebo-treated patients (see 7 WARNINGSAND PRECAUTIONS, Monitoring and Laboratory Tests, Serum Cholesterol Elevation).
These data should be taken into consideration when treating patients with underlying cardiac risk factors.
Hematologic
Abnormal Bleeding
SSRIs and serotonin / norepinephrine reuptake inhibitors (SNRIs) including MAR-PAROXETINE, may increase the risk of bleeding events by causing abnormal platelet aggregation. Concomitant use of acetylsalicylic acid (ASA), nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin and other anticoagulants may add to the risk. Case reports and epidemiological studies (case-control and cohort design) have demonstrated an association between use of drugs that interfere with serotonin reuptake and the occurrence of gastrointestinal bleeding or gynecological hemorrhage. Bleeding events related to SSRIs and SNRIs use have ranged from ecchymoses, hematomas, epistaxis, and petechiae to life- threatening haemorrhages. Gastrointestinal and gynaecological bleeding have also been reported following treatment with paroxetine hydrochloride. SSRIs/SNRIs, including MAR-PAROXETINE, may increase the risk of postpartum hemorrhage (7.1.1 Pregnant Women, Complications following late third trimester exposure to SSRIs).
Patients should be cautioned about the risk of bleeding associated with the concomitant use of MAR-PAROXETINE and NSAIDs, ASA, or other drugs that affect coagulation (see 9.4 Drug-Drug Interactions, Drugs Affecting Platelet Function). Caution is advised in patients with a history of bleeding disorder or predisposing conditions (e.g. thrombocytopenia or coagulation disorders).
Hepatic/Biliary/Pancreatic
Hepatic Impairment
Pharmacokinetic studies of paroxetine hydrochloride in subjects with clinically significant hepatic impairment suggest that prolongation of the elimination half-life and increased plasma levels can be expected in this patient group. MAR-PAROXETINE should be used with caution and dosages restricted to the lower end of the range in patients with clinically significant hepatic impairment (see 4.2 Recommended Dose and Dosage Adjustment, Special Patient Populations and 10.3 Pharmacokinetics, Hepatic Insufficiency).
Immune
Hypersensitivity
The 10 mg tablet coating contains an azo dye (FD&C Yellow No. 6 aluminium lake) which may cause allergic reactions.
Monitoring and Laboratory Tests
Serum Cholesterol Elevation
Of the patients in placebo-controlled clinical trials for whom baseline and on-treatment measurements were taken, increases from baseline of 45 mg/dL or greater were recorded in 6.6% of paroxetine-treated patients compared to 2.6% of placebo-treated patients(see 8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data, Laboratory Changes-Cholesterol and 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
These data should be taken into consideration when treating patients with underlying cardiac risk factors.
Musculoskeletal
Bone Fracture Risk
Epidemiological studies show an increased risk of bone fractures following exposure to some antidepressants, including SSRIs. The risks appear to be greater at the initial stages of treatment, but significant increased risks were also observed at later stages of treatment. The possibility of fracture should be considered in the care of patients treated with MAR-PAROXETINE. Elderly patients and patients with important risk factors for bone fractures should be advised of possible adverse events which increase the risk of falls, such as dizziness and orthostatic hypotension, especially at the early stages of treatment but also soon after withdrawal. Preliminary data from observational studies show association of SSRIs and low bone mineral density in older men and women. Until further information becomes available, a possible effect on bone mineral density with long-term treatment with SSRIs, including MAR-PAROXETINE, cannot be excluded, and may be a potential concern for patients with osteoporosis or major risk factors for bone fractures.
Neurologic
Epilepsy
As with other antidepressants, MAR-PAROXETINE should be used with caution in patients with epilepsy.
Seizures
During clinical trials, the overall incidence of seizures was 0.15% in patients treated with paroxetine hydrochloride. However, patients with a history of convulsive disorders were excluded from these studies. Caution is recommended when the drug is administered to patients with a history of seizures. The drug should be discontinued in any patient who develops seizures.
Serotonin Toxicity /Neuroleptic Malignant Syndrome
On rare occasions, serotonin toxicity, also known as serotonin syndrome, has been reported with paroxetine hydrochloride, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature > 38°C and ocular clonus or inducible clonus
Neuroleptic malignant syndrome has also been rarely reported with paroxetine hydrochloride, particularly during combined use with neuroleptic/antipsychotic drugs. The clinical manifestations of neuroleptic malignant syndrome often overlap with those of serotonin toxicity, including hyperthermia, hypertonia, altered mental status, and autonomic instability. In contrast to serotonin toxicity, patients with neuroleptic malignant syndrome may present with “lead pipe” muscle rigidity as well as hyporeflexia.
The concomitant use of MAR-PAROXETINE with monoamine oxidase inhibitors, including linezolid and methylthioninium chloride (methylene blue), is contraindicated (see 2 CONTRAINDICATIONS). MAR-PAROXETINE should be used with caution in patients receiving other serotonergic drugs or antipsychotics/neuroleptics. If concomitant treatment with MAR-PAROXETINE and other serotonergic drugs and/or antipsychotics/neuroleptics is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). Serotonin toxicity and neuroleptic malignant syndrome may result in potentially life-threatening conditions. If serotonin toxicity or neuroleptic malignant syndrome is suspected, discontinuation of MAR-PAROXETINE should be considered.
Ophthalmologic
Angle-Closure Glaucoma
As with other antidepressants, paroxetine hydrochloride can cause mydriasis, which may trigger an angle-closure attack in a patient with anatomically narrow ocular angles. Caution should be used when MAR-PAROXETINE is prescribed for patients with untreated narrow angles. Open-angle glaucoma is not a risk factor for angle-closure glaucoma. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Psychiatric
Potential Association with Behavioral and Emotional Changes, Including Self-Harm
Pediatrics: Placebo-Controlled Clinical Trial Data
- Recent analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer antidepressants suggests that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo.
- The small denominators in the clinical trial database, as well as the variability in placebo rates, preclude reliable conclusions on the relative safety profiles among these drugs.
Adult and Pediatrics: Additional data
- There are clinical trial and post-marketing reports with SSRIs and other newer antidepressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm or harm to others. The agitation-type events include: akathisia, agitation, disinhibition, emotional lability, hostility, aggression, and depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages. This includes monitoring for agitation-type emotional and behavioural changes.
An FDA meta-analysis of placebo-controlled clinical trials of antidepressant drugs in adult patients ages 18 to 24 years with psychiatric disorders showed an increased risk of suicidal behaviour with antidepressant compared to placebo.
Suicide Risk
The possibility of a suicide attempt is inherent in depression and may persist until remission occurs. Patients with depression may experience worsening of their depressive symptoms and/or the emergence of suicidal ideation and behaviours (suicidality) whether or not they are taking antidepressant medications. Notwithstanding, high risk patients should be closely supervised throughout therapy with appropriate consideration to the possible need for hospitalization. Health professionals should encourage patients of all ages, their families, and their caregivers to be alert to the emergence of any new or worsened distressing thoughts or feelings occurring at any time, and especially when initiating therapy or during any change in dose or dosage regimen. In order to minimize the opportunity for overdosage, prescriptions for MAR-PAROXETINE should be written for the smallest quantity of drug consistent with good patient management.
Because of the well established comorbidity between depression and other psychiatric disorders, the same precautions observed when treating patients with depression should be observed when treating patients with other psychiatric disorders (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioral and Emotional Changes, Including Self-Harm).
Activation of Mania/Hypomania
During clinical testing in a patient population comprised primarily of unipolar depressed patients, approximately 1% of paroxetine hydrochloride -treated patients experienced manic reactions. When bipolar patients were considered as a sub-group the incidence of mania was 2%. As with all drugs effective in the treatment of depression, MAR-PAROXETINE should be used with caution in patients with a history of mania.
A major depressive episode may be the initial presentation of bipolar disorder. Patients with bipolar disorder may be at an increased risk of experiencing manic episodes when treated with antidepressants alone. Therefore, the decision to initiate symptomatic treatment of depression should only be made after patients have been adequately assessed to determine if they are at risk for bipolar disorder.
Electroconvulsive Therapy (ECT)
The efficacy and safety of the concurrent use of paroxetine hydrochloride and ECT have not been studied.
Renal
Hyponatremia
Several cases of hyponatremia have been reported. The hyponatremia appeared to be reversible when paroxetine hydrochloride was discontinued. The majority of these occurrences have been in elderly individuals, some in patients taking diuretics or who were otherwise volume depleted.
Renal Impairment
Since paroxetine hydrochloride is extensively metabolized by the liver, excretion of unchanged drug in urine is a minor route of elimination. However, single dose pharmacokinetic studies in subjects with clinically significant renal impairment suggest that plasma levels of paroxetine are elevated in such subjects. MAR-PAROXETINE should therefore be used with caution and the dosage restricted to the lower end of the range in patients with clinically significant renal impairment (see 4.2 Recommended Dose and Dosage Adjustment and 10.3 Pharmacokinetics, Renal Insufficiency).
Reproductive Health: Female and Male Potential
Fertility
Some clinical studies have shown that SSRIs (including paroxetine hydrochloride) may affect sperm quality. This effect appears to be reversible following discontinuation of treatment. Changes in sperm quality may affect fertility in some men (see 16 NON-CLINICAL TOXICOLOGY, Reproductive and Developmental Toxicology).
Function
SSRIs may cause symptoms of sexual dysfunction (see 8 ADVERSE REACTIONS, Male and Female Sexual Dysfunction with SSRIs). Patients should be informed that there have been reports of long- lasting sexual dysfunction where the symptoms have continued despite discontinuation of SSRIs.
7.1 Special Populations
7.1.1 Pregnant Women
Risk of Cardiovascular Malformations following first trimester exposure to SSRIs
Epidemiological studies of pregnancy outcomes following maternal exposure to antidepressants in the first trimester have reported an increase in the risk of congenital malformations, particularly cardiovascular (e.g. ventricular and atrial septal defects), associated with the use of paroxetine. The data suggest that the risk of having an infant with a cardiovascular defect following maternal paroxetine exposure is approximately 1/50 (2%), compared with an expected rate for such defects of approximately 1/100 (1%) infants in the general population. In general, septal defects range from those that are symptomatic and may require surgery, to those that are asymptomatic and may resolve spontaneously. Information about the severity of the septal defects reported in the studies is not available.
While on MAR-PAROXETINE: Pregnancy, or intent to become pregnant
If a patient becomes pregnant while taking MAR-PAROXETINE, or intends to become pregnant, she should be informed of the current estimate of increased risk to the fetus with MAR-PAROXETINE over other antidepressants. Examinations of additional databases, as well as updated analyses, may result in changes to the current risk estimates. Consideration should be given to switching to other treatment options, including another antidepressant or non-pharmaceutical treatment such as cognitive behavioural therapy. Treatment with MAR-PAROXETINE should only be continued for an individual patient, if the potential benefits outweigh the potential risks.
Due to the potential for discontinuation symptoms, if a decision is taken to discontinue MAR-PAROXETINE treatment, a gradual reduction in the dose rather than an abrupt cessation is recommended (see 7 WARNINGS AND PRECAUTIONS, Discontinuation of treatment with WARNINGS AND PRECAUTIONS, Discontinuation of Treatment With Paroxetine Hydrochloride; 8 ADVERSE REACTIONS, Adverse Reactions following Discontinuation of Treatment (or Dose Reduction) and 4.1 Dosing Considerations).
Initiation of MAR-PAROXETINE: For women who intend to become pregnant, or are in their first trimester of pregnancy, initiation of paroxetine hydrochloride should be considered only after other treatment options have been evaluated.
Complications following late third trimester exposure to SSRIs
Post-marketing reports indicate that some neonates exposed to paroxetine hydrochloride, SSRIs, or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and other newer antidepressants, or, possibly, a drug discontinuation syndrome. It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome (see 7 WARNINGSAND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome).
There have been post-marketing reports of premature birth in pregnant women exposed to paroxetine or other SSRIs. The casual relationship between paroxetine hydrochloride and the emergence of these events has not been established.
Observational data have provided evidence of an increased risk (less than two-fold) of postpartum haemorrhage following SSRI/SNRI exposure within the month prior to birth (see 7 WARNINGS AND PRECAUTIONS, Hematologic).
When treating a pregnant woman with MAR-PAROXETINE during the third trimester, the health professional should carefully consider the potential risks and benefits of treatment (see 4.2 Recommended Dose and Dosage Adjustment, Special Patient Population).
Risk of Persistent Pulmonary Hypertension of the Newborn (PPHN) and exposure to SSRIs (including paroxetine)
Epidemiological studies on PPHN have shown that the use of SSRIs (including paroxetine hydrochloride) in pregnancy, particularly use in late pregnancy, was associated with an increased risk of PPHN. PPHN occurs in 1 to 2 per 1000 live births in the general population and is associated with substantial neonatal morbidity and mortality. In a retrospective case-control study of 377 women whose infants were born with PPHN and 836 women whose infants were born healthy, the risk for developing PPHN was approximately six-fold higher for infants exposed to SSRIs after the 20th week of gestation compared to infants who had not been exposed to antidepressants during pregnancy (Odds Ratio 6.1, 95% CI 2.2-16.8). A study using data from the Swedish Medical Birth Register for 831,324 infants born between 1997 and 2005 found an increased risk of PPHN of approximately 2-fold associated with patient-reported maternal use of SSRIs in the first trimester of pregnancy (Risk Ratio 2.4, 95% CI 1.2-4.3), and an increased risk of PPHN of approximately 4-fold associated with a combination of patient-reported maternal use of SSRIs in the first trimester and an antenatal SSRI prescription in later pregnancy(Risk Ratio 3.6, 95% CI 1.2-8.3).
7.1.2 Breast-feeding
The concentrations of paroxetine detected in the breast milk of lactating women are similar to those in the mother’s plasma. Lactating women should not nurse their infants while receiving paroxetine unless in the opinion of the treating health professional, breast-feeding is necessary, in which case the infant should be closely monitored.
7.1.3 Pediatrics
Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioral and Emotional Changes, Including Self-Harm). (See also 1.1 Pediatrics and 4.2 Recommended Dose and Dosage Adjustment, Pediatrics).
Controlled clinical studies in depression failed to demonstrate efficacy and do not support the use of paroxetine in the treatment of children under the age of 18 years with depression. Moreover, a higher incidence of adverse events related to behavioural and emotional changes, including self harm, was reported with paroxetine treatment compared to placebo during controlled clinical trials in depression, OCD and social anxiety disorder (see 8.2.1 Clinical Trial Adverse Drug Reactions – Pediatrics).
7.1.4 Geriatrics
Geriatrics (≥ 65 years of age): Administration of paroxetine hydrochloride to the elderly is associated with increased plasma levels and prolongation of the elimination half life relative to younger adults (see 10 CLINICAL PHARMACOLOGY). Elderly patients should be initiated and maintained at the lowest daily dose of paroxetine which is associated with clinical efficacy (see 4 DOSAGE AND ADMINISTRATION).
Evaluation of approximately 800 elderly patients (≥ 65 years) treated with paroxetine hydrochloride (10 to 40 mg daily) in worldwide premarketing clinical trials revealed no unusual pattern of adverse events relative to the clinical experience in younger patients. However, it is not possible to rule out potential age-related differences in safety and effectiveness during chronic use, particularly in elderly patients who have concomitant systemic illnesses or who are receiving concomitant drugs.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview Commonly Observed Adverse Events
The most commonly observed adverse experiences associated with the use of paroxetine hydrochloride in clinical trials and not seen at an equivalent incidence among placebo-treated patients were: nausea, somnolence, sweating, tremor, asthenia, dizziness, dry mouth, insomnia, constipation, diarrhea, decreased appetite and male sexual dysfunction (see Table 2 and Table 3).
Adverse Events Leading to Discontinuation of Treatment
Twenty-one percent of over 4000 patients who received paroxetine hydrochloride in worldwide clinical trials in depression discontinued treatment due to an adverse experience. In obsessive-compulsive disorder, panic disorder, social phobia (social anxiety disorder), generalized anxiety disorder and posttraumatic stress disorder studies, 11.8% (64/542), 9.4% (44/469), 16.1% (84/522), 10.7% (79/735) and 11.7% (79/676), respectively, of patients treated with paroxetine hydrochloride discontinued treatment because of adverse events. The most common events leading to discontinuation (reported by 1% or more of subjects) included: asthenia, headache, nausea, somnolence, insomnia, agitation, tremor, dizziness, constipation, impotence, abnormal ejaculation, sweating and diarrhea.
Adverse Events following Discontinuation of Treatment (or Dose Reduction)
- Clinical Trials
The following adverse events have been reported at an incidence of 2% or greater for paroxetine hydrochloride and were at least twice that reported for placebo: abnormal dreams (2.3 vs 0.5%), paresthesias (2.0 vs 0.4%), and dizziness (7.1 vs 1.5%).
The majority of these events were mild to moderate, self-limiting and did not require medical intervention. These adverse events were noted in GAD and PTSD clinical trials employing a taper phase regimen for discontinuation of treatment. This regimen involved an incremental decrease in the daily dose by 10 mg/day at weekly intervals. When a daily dose of 20 mg/day was reached, patients were continued on this dose for 1 week before treatment was stopped.
- Post-Marketing
There have been spontaneous reports of adverse events upon the discontinuation of paroxetine hydrochloride (particularly when abrupt), including but not limited to the following: dizziness, sensory disturbances (including paresthesias, electric shock sensations and tinnitus), agitation/restlessness, anxiety, nausea, tremor, confusion, diarrhea, vomiting, sweating, headache, and sleep disturbances (abnormal dreams). Generally, these symptoms are mild to moderate, however, in some patients they may be severe in intensity. They usually occur within the first few days of discontinuing treatment, but there have been very rare reports of such symptoms in patients who have inadvertently missed a dose. Generally, these symptoms are self-limiting and usually resolve within 2 weeks, though in some individuals they may be prolonged (2 to 3 months or more). Symptoms associated with discontinuation have been reported for other selective serotonin reuptake inhibitors.
Patients should be monitored for these or any other symptoms when discontinuing treatment, regardless of the indication for which MAR-PAROXETINE is being prescribed. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, dose titration should be managed on the basis of the patient’s clinical response (see 7 WARNINGS AND PRECAUTIONS and 4 DOSAGE AND ADMINISTRATION).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Incidence in Controlled Clinical Trials
Multiple doses of paroxetine hydrochloride were administered to 4126 subjects in clinical trials for depression, 542 subjects in clinical trials for OCD, 469 subjects in clinical trials for panic disorder, 522 subjects in clinical trials for social phobia (social anxiety disorder), 735 subjects in clinical trials for generalized anxiety disorder and 676 subjects in clinical trials for posttraumatic stress disorder. Untoward experiences associated with this exposure were recorded by clinical investigators using descriptive terminology of their own choosing. Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse experiences without first grouping similar types of untoward experiences into a limited (i.e. reduced) number of standardized experience categories.
Table 2 lists adverse experiences that occurred at an incidence of 1% or higher in short-term (6-week) flexible dose (20 to 50 mg/day) placebo-controlled trials in depression. (An additional 460 patients participated in a fixed-dose, placebo-controlled study).
Table 3 enumerates adverse events that occurred at a frequency of 2% or more among patients on paroxetine hydrochloride who participated in placebo-controlled OCD trials of 12-weeks duration in which patients were dosed in the range of 20 to 60 mg/day, in placebo-controlled panic disorder trials of 10 to 12 weeks duration in which patients were dosed in the range of 10 to 60 mg/day, in placebo-controlled social phobia (social anxiety disorder) trials of 12 weeks duration in which patients were dosed in a range of 20 to 50 mg/day, in placebo-controlled generalized anxiety disorder trials of 8 weeks in which patients were dosed in a range from 10 to 50 mg/day and in placebo-controlled posttraumatic stress disorder trials of 12 weeks in which patients were dosed in a range from 20 to 50 mg/day.
The prescriber should be aware that these figures cannot be used to predict the incidence of side effects in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials. Similarly the cited incidences cannot be compared with figures obtained from other clinical investigations involving different treatments, uses and investigators. The cited frequencies do however provide the prescribing health professional with some basis for estimating the relative contribution of drug and non-drug factors to the side effect incidence rate in the population studied. Reported adverse experiences were classified using a COSTART-based dictionary terminology for the depression trials and an ADECS (a modified COSTART dictionary) for OCD and panic disorder trials.
Table 2 Treatment-Emergent Adverse Events in Short Term Flexible Dose Placebo-Controlled Clinical Trials in Depression1
| Body System | Preferred Term | Paroxetine (n=421) | Placebo (n=421) |
|---|---|---|---|
| Body as a Whole | Headache | 17.6% | 17.3% |
| Asthenia | 15.0% | 5.9% | |
| Abdominal Pain | 3.1% | 4.0% | |
| Fever | 1.7% | 1.7% | |
| Chest Pain | 1.4% | 2.1% | |
| Trauma | 1.4% | 0.5% | |
| Back Pain | 1.2% | 2.4% | |
| Cardiovascular | Palpitation | 2.9% | 1.4% |
| Vasodilation | 2.6% | 0.7% | |
| Postural Hypotension | 1.2% | 0.5% | |
| Dermatological | Sweating | 11.2% | 2.4% |
| Rash | 1.7% | 0.7% | |
| Gastrointestinal | Nausea | 25.7% | 9.3% |
| Dry Mouth | 18.1% | 12.1% | |
| Constipation | 13.8% | 8.6% | |
| Diarrhea | 11.6% | 7.6% | |
| Decreased Appetite | 6.4% | 1.9% | |
| Flatulence | 4.0% | 1.7% | |
| Vomiting | 2.4% | 1.7% | |
| Oropharynx Disorder2 | 2.1% | 0.0% | |
| Dyspepsia | 1.9% | 1.0% | |
| Increased Appetite | 1.4% | 0.5% | |
| Musculoskeletal | Myopathy | 2.4% | 1.4% |
| Myalgia | 1.7% | 0.7% | |
| Myasthenia | 1.4% | 0.2% | |
| Nervous System | Somnolence | 23.3% | 9.0% |
| Dizziness | 13.3% | 5.5% | |
| Insomnia | 13.3% | 6.2% | |
| Tremor | 8.3% | 1.9% | |
| Nervousness | 5.2% | 2.6% | |
| Anxiety | 5.0% | 2.9% | |
| Paraesthesia | 3.8% | 1.7% | |
| Libido Decreased | 3.3% | 0.0% | |
| Agitation | 2.1% | 1.9% | |
| Drugged Feeling | 1.7% | 0.7% | |
| Myoclonus | 1.4% | 0.7% | |
| CNS Stimulation | 1.2% | 3.6% | |
| Confusion | 1.2% | 0.2% | |
| Respiration | Respiratory Disorder3 | 5.9% | 6.4% |
| Yawn | 3.8% | 0.0% | |
| Pharyngitis | 2.1% | 2.9% |
Table 2 (cont’d) Treatment-Emergent Adverse Events in Short Term Flexible Dose Placebo-Controlled Clinical Trials in Depression1
| Body System | Preferred Term | Paroxetine (n=421) | Placebo (n=421) |
|---|---|---|---|
| Special Senses | Blurred Vision | 3.6% | 1.4% |
| Taste Perversion | 2.4% | 0.2% | |
| Urogenital System | *Abnormal Ejaculation+ | 12.9% | 0.0% |
| *Male Genital Disorders4 | 8.0% | 0.0% | |
| Urinary Frequency | 3.1% | 0.7% | |
| Urination Impaired5 | 2.9% | 0.2% | |
| *Impotence | 2.5% | 0.5% | |
| *Female Genital Disorders6 | 1.8% | 0.0% |
1 Events reported by at least 1% of patients treated with paroxetine hydrochloride are included.
* Percentage corrected for gender Placebo: male, n=206 female, n=215 Paroxetine: male, n=201 female, n=220
+ Primarily ejaculatory delay. In a trial of fixed doses of paroxetine, the incidence of ejaculatory disturbance in males with 20 mg per day of paroxetine was 6.5% (3/46) versus 0% (0/23) in the placebo group.
2 Includes mostly lump in throat and tightness in throat
3 Includes mostly cold symptoms or URI
4 Includes anorgasmia, erectile difficulties, delayed ejaculation/orgasm, sexual dysfunction and impotence
5 Includes difficulty with micturition and urinary hesitancy
6 Includes anorgasmia and difficulty reaching climax/orgasm
Table 3 Treatment-Emergent Adverse Experience Incidence in Placebo-Controlled Clinical Trials for Obsessive-Compulsive Disorder, Panic Disorder, Social Phobia (Social Anxiety Disorder), Generalized Anxiety Disorder and Posttraumatic Stress Disorder. 1
| Body System | Preferred Term | Obsessive- Compulsive Disorder | Panic Disorder | Social Phobia (Social Anxiety Disorder) | Generalized Anxiety Disorder | Posttraumatic Stress Disorder | |||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| MAR-PAROX ETINE (n=542) | Placebo (n=265) | MAR-PAROX ETINE (n=469) | Placebo (n=324) | MAR-PAROX ETINE (n=425) | Placebo (n=339) | MAR-PAROX ETINE (n=735) | Placebo (n=529) | MAR-PAROX ETINE (n=676) | Placebo (n=504) | ||||||||||||||
Body as a Whole | Headache | 25.3% | 29.1% | 25.4% | 25.3% | 22.4% | 21.8% | 16.9% | 14.0% | 18.9% | 19.2% | ||||||||||||
| Asthenia | 21.8% | 13.6% | 13.6% | 4.6% | 22.4% | 13.6% | 14.3% | 6.4% | 11.8% | 4.2% | |||||||||||||
| Infection | 5.4% | 4.9% | 5.3% | 6.8% | 3.8% | 5.9% | 5.6% | 3.4% | 4.9% | 3.8% | |||||||||||||
| Abdominal Pain | 4.8% | 4.9% | 4.3% | 3.1% | 2.1% | 4.7% | 4.5% | 3.6% | 4.3% | 3.2% | |||||||||||||
| Chest Pain | 2.8% | 1.9% | 2.3% | 3.1% | 0.7% | 0.3% | 1.0% | 0.6% | 1.2% | 0.8% | |||||||||||||
| Back Pain | 2.4% | 4.9% | 3.2% | 2.2% | 1.6% | 4.1% | 2.3% | 3.6% | 3.4% | 3.4% | |||||||||||||
| Chills | 2.0% | 0.8% | 2.3% | 0.6% | 0.2% | 0.3% | 1.0% | 0.0% | 0.1% | 0.4% | |||||||||||||
| Trauma | 3.1% | 3.8% | 3.6% | 3.7% | 2.6% | 0.9% | 2.6% | 3.4% | 5.8% | 5.2% | |||||||||||||
| Cardio- vascular | Vasodilation | 3.9% | 1.1% | 2.1% | 2.8% | 1.4% | 0.6% | 2.7% | 0.8% | 2.2% | 1.2% | ||||||||||||
| Palpitation | 2.0% | 0.4% | 2.3% | 2.5% | 1.2% | 1.8% | 1.1% | 1.1% | 1.0% | 0.8% | |||||||||||||
| Dermatologic | Sweating | 8.9% | 3.0% | 14.3% | 5.9% | 9.2% | 2.1% | 6.3% | 1.5% | 4.6% | 1.4% | ||||||||||||
| Rash | 3.1% | 1.9% | 2.3% | 1.5% | 0.7% | 0.3% | 1.5% | 0.9% | 1.5% | 2.0% | |||||||||||||
| Gastro- intestinal | Nausea | 23.2% | 9.8% | 22.8% | 17.3% | 24.7% | 6.5% | 20.1% | 5.3% | 19.2% | 8.3% | ||||||||||||
| Dry Mouth | 18.1% | 8.7% | 18.1% | 10.8% | 8.9% | 2.9% | 10.9% | 4.7% | 10.1% | 4.8% | |||||||||||||
| Constipation | 15.7% | 6.4% | 7.9% | 5.2% | 5.4% | 1.8% | 10.5% | 1.7% | 5.5% | 3.4% | |||||||||||||
| Diarrhea | 10.3% | 9.8% | 11.7% | 6.5% | 8.5% | 5.9% | 9.1% | 6.6% | 10.5% | 5.4% | |||||||||||||
| Decreased Appetite | 9.0% | 3.4% | 7.0% | 2.8% | 7.8% | 1.5% | 5.2% | 1.1% | 5.9% | 2.6% | |||||||||||||
| Dyspepsia | 3.9% | 6.8% | 3.8% | 6.8% | 4.0% | 2.4% | 4.5% | 4.9% | 4.6% | 3.4% | |||||||||||||
| Flatulence | 3.0% | 4.2% | 1.7% | 2.8% | 4.0% | 2.4% | 1.4% | 2.1% | 1.0% | 1.0% | |||||||||||||
| Increased Appetite | 4.2% | 3.0% | 2.1% | 0.6% | 1.2% | 1.8% | 0.4% | 1.1% | 1.5% | 1.0% | |||||||||||||
| Vomiting | 2.2% | 3.4% | 1.9% | 1.5% | 2.4% | 0.6% | 2.7% | 2.5% | 3.0% | 2.0% | |||||||||||||
| Musculo- skeletal Nervous System | Myalgia | 3.1% | 3.8% | 2.3% | 3.4% | 4.0% | 2.7% | 2.9% | 2.6% | 1.8% | 1.8% | ||||||||||||
| Somnolence | 24.4% | 7.2% | 18.8% | 10.8% | 21.6% | 5.3% | 15.4% | 4.5% | 16.0% | 4.6% | |||||||||||||
| Insomnia | 23.8% | 13.2% | 17.9% | 10.2% | 20.9% | 15.9% | 10.7% | 7.9% | 11.8% | 11.3% | |||||||||||||
| Dizziness | 12.4% | 6.0% | 14.1% | 9.9% | 11.3% | 7.1% | 6.1% | 4.5% | 6.1% | 4.6% | |||||||||||||
| Tremor | 10.5% | 1.1% | 8.5% | 1.2% | 8.7% | 1.2% | 4.6% | 0.8% | 4.3% | 1.4% | |||||||||||||
| Nervousness | 8.5% | 8.3% | 7.9% | 8.3% | 7.5% | 6.5% | 3.9% | 2.8% | 3.0% | 4.4% | |||||||||||||
| Libido Decreased | 7.2% | 3.8% | 8.5% | 1.2% | 11.5% | 0.9% | 9.4% | 1.5% | 5.2% | 1.8% | |||||||||||||
| Anxiety | 4.1% | 6.8% | 4.5% | 4.0% | 4.7% | 4.1% | 1.6% | 0.9% | 3.8% | 4.0% | |||||||||||||
| Abnormal Dreams | 3.9% | 1.1% | 2.8% | 3.4% | 1.9% | 1.5% | 0.5% | 1.1% | 2.5% | 1.6% | |||||||||||||
| Myoclonus | 3.3% | 0.4% | 3.2% | 1.5% | 2.1% | 0.9% | 1.6% | 0.6% | 1.0% | 0.6% | |||||||||||||
| Concentration Impaired | 2.8% | 1.5% | 1.1% | 0.9% | 3.5% | 0.6% | 1.1% | 0.6% | 1.5% | 1.0% | |||||||||||||
| Depersonalization | 2.6% | 0.4% | 1.7% | 2.2% | 0.7% | 0.9% | 0.7% | 0.0% | 0.9% | 0.2% | |||||||||||||
| Amnesia | 2.2% | 1.1% | 0.6% | 0.0% | 0.5% | 0.3% | 0.4% | 0.6% | 1.3% | 1.0% | |||||||||||||
| Hyperkinesia | 2.2% | 1.5% | 0.9% | 0.9% | 1.2% | 0.0% | 0.8% | 0.0% | 1.3% | 0.2% | |||||||||||||
| Agitation | 1.7% | 2.3% | 4.7% | 3.7% | 2.6% | 0.9% | 1.8% | 1.1% | 1.9% | 3.2% | |||||||||||||
Table 3 (cont’d) Treatment-Emergent Adverse Experience Incidence in Placebo-Controlled Clinical Trials for Obsessive-Compulsive Disorder, Panic Disorder, Social Phobia (Social Anxiety Disorder), Generalized Anxiety Disorder and Posttraumatic Stress Disorder .1
| Body System | Preferred Term | Obsessive- Compulsive Disorder | Panic Disorder | Social Phobia (Social Anxiety Disorder) | Generalized Anxiety Disorder | Posttraumatic Stress Disorder | ||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| MAR-PAROX ETINE (n=542) | Placebo (n=265) | MAR-PAROX ETINE (n=469) | Placebo (n=324) | MAR-PAROX ETINE (n=425) | Placebo (n=339) | MAR-PAROX ETINE (n=735) | Placebo (n=529) | MAR-PAROX ETINE (n=676) | Placebo (n=504) | |||||||||||||||||||
| Respiratory System | Pharyngitis | 3.7% | 4.9% | 3.2% | 3.1% | 3.8% | 2.1% | 2.3% | 2.1% | 2.4% | 2.2% | |||||||||||||||||
| Rhinitis | 1.5% | 3.4% | 2.6% | 0.3% | 1.2% | 3.2% | 1.5% | 1.1% | 1.0% | 2.0% | ||||||||||||||||||
| Sinusitis | 1.5% | 4.9% | 5.8% | 4.6% | 2.1% | 2.4% | 3.5% | 3.4% | 3.8% | 4.4% | ||||||||||||||||||
| Yawn | 1.7% | 0.4% | 1.9% | 0.0% | 4.9% | 0.3% | 4.2% | 0.2% | 2.1% | 0.2% | ||||||||||||||||||
| Cough Increased | 1.1% | 1.9% | 2.3% | 1.5% | 0.7% | 0.9% | 0.8% | 0.8% | 1.2% | 0.6% | ||||||||||||||||||
| Respiratory Disorder1 | - | - | - | - | - | - | 6.8% | 5.1% | 3.3% | 1.0% | ||||||||||||||||||
Special Senses | Abnormal Vision | 3.7% | 2.3% | 3.0% | 2.8% | 4.0% | 0.3% | 2.2% | 0.6% | 0.3% | 0.0% | |||||||||||||||||
| Taste Perversion | 2.0% | 0.0% | 1.1% | 0.6% | 0.7% | 0.6% | 0.7% | 0.8% | 0.7% | 0.8% | ||||||||||||||||||
Urogenital System | Abnormal Ejaculation2 | 23.3% | 1.3% | 20.5% | 0.9% | 27.6% | 1.1% | 24.7% | 2.0% | 12.6% | 1.6% | |||||||||||||||||
| Dysmenorrhea2 | 1.4% | 1.9% | 2.0% | 2.3% | 4.6% | 4.4% | 1.3% | 1.2% | 1.6% | 1.3% | ||||||||||||||||||
| Impotence2 | 8.2% | 1.3% | 5.4% | 0.0% | 5.3% | 1.1% | 4.2% | 3.0% | 9.2% | 0.5% | ||||||||||||||||||
| Female Genital Disorder2,3 | 3.3% | 0.0% | 8.9% | 0.5% | 8.6% | 0.6% | 4.4% | 0.6% | 4.8% | 0.6% | ||||||||||||||||||
| Urinary Frequency | 3.3% | 1.1% | 2.1% | 0.3% | 1.6% | 1.8% | 1.0% | 0.6% | 1.0% | 0.2% | ||||||||||||||||||
Urination Impaired | 3.3% | 0.4% | 0.4% | 0.3% | 1.9% | 0.0% | 1.0% | 0.0% | 0.6% | 0.0% | ||||||||||||||||||
| Urinary Tract Infection | 1.5% | 1.1% | 2.1% | 1.2% | 0.2% | 1.2% | 1.2% | 1.1% | 0.6% | 0.8% | ||||||||||||||||||
- 1. Events reported by at least 2% of either OCD, Panic Disorder, Social Phobia (Social Anxiety Disorder), Generalized Anxiety Disorder or Posttraumatic Stress Disorder MAR-PAROXETINE-treated patients are included, except the following events which had an incidence on placebo ≥ MAR-PAROXETINE: [OCD]: depression, paraesthesia, and respiratory disorder. [Panic Disorder]: flu syndrome, depression, paraesthesia, respiratory disorder. [Social Phobia (Social Anxiety Disorder)]: depression, respiratory disorder. [Generalized Anxiety Disorder]: not applicable, [Posttraumatic Stress Disorder]: depression, respiratory disorder
- 2.
Incidence is gender-corrected.
OCD: Placebo: male, n=158; female, n=107 Paroxetine: male, n=330; female, n=212
PANIC: Placebo: male, n=111; female, n=213 Paroxetine: male, n=166; female, n=303
SOCIAL PHOBIA: Placebo: male, n=180; female, n=159
(SOCIAL ANXIETY DISORDER) Paroxetine: male, n=228; female, n=197
GENERALIZED ANXIETY DISORDER: Placebo: male, n=197; female, n=332
Paroxetine: male, n=283; female, n=452
POSTTRAUMATIC STRESS DISORDER Placebo: male, n=190; female, n=314
Paroxetine: male, n=238; female, n=438
- 3. Includes anorgasmia and difficulty reaching climax/orgasm
Male and Female Sexual Dysfunction with SSRIs
Although changes in sexual desire, sexual performance and sexual satisfaction often occur as manifestations of a psychiatric disorder, they may also be a consequence of pharmacologic treatment. In particular, some evidence suggests that SSRIs can cause such untoward sexual experiences. Furthermore, there have been reports of long-lasting sexual dysfunction where these symptoms have continued despite discontinuation of SSRIs.
Reliable estimates of the incidence and severity of untoward experiences involving sexual desire, performance and satisfaction are difficult to obtain, however, in part because patients and health professionals may be reluctant to discuss them. Accordingly, estimates of the incidence of untoward sexual experience and performance cited in product labeling are likely to underestimate their actual incidence.
- Incidence of Sexual Adverse Events in Pooled Data
In placebo-controlled clinical trials involving more than 3,200 patients, the ranges for the reported incidence of sexual side effects in males and females with major depressive disorder, OCD, panic disorder, social anxiety disorder, GAD and PTSD are displayed in Table 4 below.
Table 4 Incidence of Sexual Adverse Events in Controlled Clinical Trials
| Paroxetine | Placebo | |
|---|---|---|
| n (males) | 1446 | 1042 |
| Decreased Libido | 6-15% | 0-5% |
| Ejaculatory Disturbance | 13-28% | 0-2% |
| Impotence | 2-9% | 0-3 % |
| n (females) | 1822 | 1340 |
| Decreased Libido | 0-9% | 0-2% |
| Orgasmic Disturbance | 2-9% | 0-1% |
There are no adequate and well-controlled studies examining sexual dysfunction with paroxetine treatment.
Paroxetine treatment has been associated with several cases of priapism. In those cases with a known outcome, patients recovered without sequelae.
While it is difficult to know the precise risk of sexual dysfunction associated with the use of SSRIs, and health professionals should routinely inquire about such possible side effects.
8.2.1 Clinical Trial Adverse Reactions – Pediatrics
In placebo-controlled clinical trials conducted with pediatric patients aged 7 to 18 years with depression, OCD and Social Anxiety Disorder (involving 633 patients treated with paroxetine and 542 patients treated with placebo), the following adverse events were reported in at least 2% of pediatric patients treated with paroxetine hydrochloride and occurred at a rate at least twice that for pediatric patients receiving placebo: emotional lability (including self-harm, suicidal thoughts, attempted suicide, crying, and mood fluctuations), hostility, (predominantly aggression, oppositional behaviour and anger) decreased appetite, tremor, sweating, hyperkinesia, and agitation (see 7 WARNINGS AND PRECAUTIONS, Potential Association with Behavioral and Emotional Changes, Including Self-Harm).
In the pediatric clinical trials in depression, OCD and Social Anxiety Disorder that included a taper phase regimen (307 patients aged 7 to 18 years treated with paroxetine and 291 patients treated with placebo), events reported upon discontinuation of treatment, which occurred in at least 2% of patients who received paroxetine hydrochloride and which occurred at a rate at least twice that of placebo, were: emotional lability (including suicidal ideation, suicide attempt, mood changes, and tearfulness), nervousness, dizziness, nausea, and abdominal pain (see 7 WARNINGS AND PRECAUTIONS, Discontinuation of treatment with Paroxetine Hydrochloride).
8.3 Less Common Clinical Trial Adverse Reactions
Other Events Observed During the Clinical Development of Paroxetine
In the tabulations, which follow, a COSTART or modified COSTART-based dictionary terminology has been used to classify reported adverse experiences. The frequencies presented therefore represent the portion of the 4126, 542, 469, 522, 735 and 676 paroxetine hydrochloride exposed individuals in depression, OCD, panic, social phobia (social anxiety disorder), generalized anxiety disorder and posttraumatic stress disorder trials, respectively, who experienced an event of the type cited on at least one occasion while receiving paroxetine hydrochloride. Experiences are further classified within body system categories and enumerated in order of decreasing frequency using the following definitions: frequent experiences are defined as those occurring on one or more occasion in at least 1/100 patients; infrequent adverse experiences are those occurring in less than 1/100 but at least 1/1000 patients; rare experiences are those occurring in less than 1/1000 patients.
All adverse experiences are included except those already listed in Table 2 and Table 3 , those reported in terms so general as to be uninformative and those experiences for which the drug cause was remote. It is important to emphasize that although the experiences reported did occur during treatment with paroxetine hydrochloride, they were not necessarily caused by it.
Body as a Whole
- Frequent: Malaise, pain.
- Infrequent: Allergic reaction, chills, face edema, infection, moniliasis, neck pain, overdose.
- Rare: Abnormal laboratory value, abscess, adrenergic syndrome, cellulitis, chills and fever, cyst, hernia, intentional overdose, neck rigidity, pelvic pain, peritonitis, substernal chest pain, sepsis, ulcer.
Cardiovascular System
- Frequent: Hypertension, syncope, tachycardia.
- Infrequent: Bradycardia, conduction abnormalities, electrocardiogram abnormal, hypotension, migraine, ventricular extrasystoles.
- Rare: Angina pectoris, arrhythmia, atrial arrhythmia, atrial fibrillation, bundle branch block, cardiac disorder, cerebral ischemia, cerebrovascular accident, cerebrovascular disorder, congestive heart failure, extrasystoles, low cardiac output, myocardial infarct, myocardial ischemia, pallor, phlebitis, pulmonary embolus, supraventricular extrasystoles, thrombosis, varicose vein, vascular disorder, vascular headache.
Dermatological
- Frequent: Pruritus.
- Infrequent: Acne, alopecia, dry skin, ecchymosis, eczema, furunculosis, herpes simplex, urticaria.
- Rare: Angioedema, contact dermatitis, erythema nodosum, exfoliative dermatitis, herpes zoster, maculopapular rash, photosensitivity, skin discolouration, skin ulcer, skin hypertrophy, sweating decreased.
- Very rare: Severe cutaneous adverse reactions (including erythema multiforme, Stevens-Johnson syndrome and toxic epidermal necrolysis).
Endocrine
- Rare: Diabetes mellitus, fertility decreased female, goiter, hyperthyroidism, hypothyroidism, thyroiditis.
Gastrointestinal
- Frequent: Nausea and vomiting.
- Infrequent: Bruxism, buccal cavity disorders, dysphagia, eructation, gastroenteritis, gastrointestinal flu, glossitis, increased salivation, liver function tests abnormal, mouth ulceration, vomiting and diarrhea, rectal hemorrhage.
- Rare: Aphthous stomatitis, bloody diarrhea, bulimia, cardiospasm, colitis, duodenitis, esophagitis, fecal impaction, fecal incontinence, gastritis, gingivitis, hematemesis, hepatitis, ileitis, ileus, jaundice, melena, peptic ulcer, salivary gland enlargement, sialadenitis, stomach ulcer, stomatitis, tongue edema, tooth caries.
Hematologic and Lymphatic
- Infrequent: Anemia, leukopenia, lymphadenopathy, purpura, WBC abnormality.
- Rare: Abnormal bleeding, predominately of the skin and mucous membranes, bleeding time increased, eosinophilia, iron deficiency anemia, leukocytosis, lymphedema, lymphocytosis, microcytic anemia, monocytosis, normocytic anemia, thrombocytopenia.
Immune System Disorders:
- Very rare: Severe allergic reactions (including anaphylactoid reactions and angioedema).
Metabolic and Nutritional
- Frequent: Weight gain, weight loss, increases in cholesterol levels.
- Infrequent: Edema, hyperglycemia, peripheral edema, thirst.
- Rare: Alkaline phosphatase increased, bilirubinemia, cachexia, dehydration, gout, hypocalcemia, hypoglycemia, hypokalemia, hyponatremia (predominantly in the elderly) which is sometimes due to syndrome of inappropriate anti-diuretic hormone secretion (SIADH), non- protein nitrogen (NPN) increased, obesity, SGOT increased, SGPT increased.
Musculoskeletal
- Infrequent: Arthralgia, arthritis, traumatic fracture.
- Rare: Arthrosis, bone disorder, bursitis, cartilage disorder, myositis, osteoporosis, tetany.
Nervous System
- Frequent: CNS stimulation, concentration impaired, depression, emotional lability, vertigo.
- Infrequent: Akinesia, alcohol abuse, amnesia, ataxia, convulsion, depersonalization, hallucinations, hyperkinesia, hypertonia, incoordination, lack of emotion, manic reaction, paranoid reaction, thinking abnormal, hypesthesia.
- Rare: Abnormal electroencephalogram, abnormal gait, antisocial reaction, brain edema, choreoathetosis, circumoral paraesthesia, confusion, delirium, delusions, diplopia, drug dependence, dysarthria, dyskinesia, dystonia, euphoria, fasciculations, grandmal convulsion, hostility, hyperalgesia, hypokinesia, hysteria, libido increased, manic depressive reaction, meningitis, myelitis, neuralgia, neuropathy, nystagmus, psychosis, psychotic depression, reflexes increased, stupor, torticollis, withdrawal syndrome.
Respiratory System
- Frequent: Cough increased, rhinitis.
- Infrequent: Asthma, bronchitis, dyspnea, epistaxis, hyperventilation, pneumonia, respiratory flu, sinusitis.
- Rare: Hiccup, lung fibrosis, sputum increased, stridor, trachea disorder, voice alteration.
Special Senses
- Infrequent: Abnormality of accommodation, conjunctivitis, ear pain, eye pain, mydriasis, otitis media, tinnitus.
Rare: Amblyopia, cataract specified, conjunctival edema, corneal lesion, corneal ulcer,
exophthalmos, eye hemorrhage, acute glaucoma, hyperacusis, otitis externa, photophobia, retinal hemorrhage, taste loss, anisocoria, deafness, keratoconjunctivitis.
Urogenital system
- Infrequent: Abortion*, amenorrhea*, breast pain*, cystitis, dysmenorrhea*, dysuria, menorrhagia*, nocturia, polyuria, urinary incontinence, urinary retention, urinary tract infection, urinary urgency, vaginitis*.
Rare: Breast atrophy*, cervix disorder*, endometrial disorder*, female lactation*, hematuria, kidney calculus, kidney function abnormal, kidney pain, mastitis*, nephritis, oliguria, salpingitis*, spermatogenesis arrest* urethritis, urinary casts, urine abnormality, uterine neoplasm*, vaginal moniliasis*.
* Incidence corrected for gender.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data Laboratory Changes - Cholesterol
Clinically and statistically relevant increases in cholesterol levels have been noted in studies using paroxetine (see 7 WARNINGS AND PRECAUTIONS, Endocrine and Metabolism).
Of the patients in placebo-controlled clinical trials for whom baseline and on-treatment measurements were taken, total serum levels of cholesterol showed a mean increase of ~ 1.5 mg/dL in paroxetine- treated patients (n = 653), compared to a mean decrease of ~ 5.0 mg/dL in placebo-treated patients (n= 379). Increases from baseline of 45 mg/dL or greater were recorded in 6.6% of paroxetine-treated patients compared to 2.6% of placebo-treated patients.
8.5 Post-Market Adverse Reactions
Adverse events not listed above which have been reported since market introduction in patients taking paroxetine hydrochloride include: acute pancreatitis, hepatic events such as elevation of hepatic enzymes, and hepatitis, sometimes associated with jaundice, and/or liver failure (in very rare circumstances, with fatal outcomes), Guillain-Barré syndrome, priapism, thrombocytopenia, aggravated hypertension, syndrome of inappropriate ADH secretion, symptoms suggestive of hyperprolactinemia and galactorrhea, menstrual disorders (including menorrhagia, metrorrhagia and amenorrhea), blurred vision; extrapyramidal symptoms which have included akathisia, (characterized by an inner sense of restlessness and psychomotor agitation such as an inability to sit or stand still usually associated with subjective distress), bradykinesia, cogwheel rigidity, dystonia, hypertonia, oculogyric crisis which has been associated with concomitant use of pimozide, tremor and trismus, abnormal dreams (including nightmares), restless legs syndrome (RLS), neuroleptic malignant syndrome-like events and serotonin syndrome (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome), persistent pulmonary hypertension (see also 7.1.1 Pregnant Women, Risk of PPHN and exposure to SSRIs). There has been a case report of an elevated phenytoin level after 4 weeks of paroxetine hydrochloride and phenytoin co-administration.
There has been a case report of severe hypotension when paroxetine hydrochloride was added to chronic metoprolol treatment. The causal relationship between paroxetine hydrochloride and the emergence of these events has not been established.
There have been spontaneous reports of adverse events upon the discontinuation of paroxetine hydrochloride and other selective serotonin reuptake inhibitors (particularly when abrupt) (see 7 WARNINGS AND PRECAUTIONS, Discontinuation of treatment with Paroxetine Hydrochloride and 8 ADVERSE REACTIONS, Adverse Events following Discontinuation of Treatment (or Dose Reduction)).
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
Like some other selective serotonin re-uptake inhibitors, paroxetine inhibits the specific hepatic cytochrome P450 isozyme CYP2D6 which is responsible for the metabolism of debrisoquine and sparteine. Poor metabolizers of debrisoquine/sparteine represent approximately 5 to 10% of Caucasians. The median Cmin (ss) for paroxetine hydrochloride (20 mg daily) at steady state in poor metabolizers (n=8) was almost triple that reported for extensive metabolizers (n=9). Although the full clinical significance of this effect has not been established, inhibition of CYP2D6 can lead to elevated plasma levels of co- administered drugs which are metabolized by this isozyme. Consideration should be given to decreasing the dose of the CYP2D6 metabolized drug or paroxetine and/or monitoring of drug plasma levels, especially when paroxetine hydrochloride is co-administered with drugs with a narrow therapeutic index.
Paroxetine hydrochloride co-administration has been associated with elevated levels of the anti-cholinergic procyclidine, certain neuroleptics/antipsychotics (e.g. perphenazine, risperidone), tricyclic antidepressants (e.g. desipramine), atomoxetine, type 1C antiarrhythmics (e.g. propafenone), and theophylline.
Co-administration of phenobarbitol or phenytoin with paroxetine hydrochloride has been associated with decreased levels of paroxetine hydrochloride. When co-administered with cimetidine, paroxetine hydrochloride levels were elevated.
9.3 Drug-Behavioural Interactions
Alcohol: The concomitant use of paroxetine hydrochloride and alcohol has not been studied and is not recommended. Patients should be advised to avoid alcohol while taking paroxetine hydrochloride.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Serious Drug Interactions
MAR-PARAOXETINE is contraindicated with:
- Monoamine Oxidase Inhibitors: Combined use of MAR-PARAOXETINE and monoamine oxidase inhibitors (MAOIs) [including linezolid, an antibiotic which is a reversible non-selective MAOI and methylthioninium chloride (methylene blue)] is contraindicated due to the potential for serious reactions with features resembling serotonin syndrome or neuroleptic malignant syndrome.
- Thioridazine: Thioridazine administration alone produces prolongation of the QTc interval, which is associated with serious ventricular arrhythmias, such as torsade de pointes-type arrhythmias, and sudden death. This effect appears to be dose-related and paroxetine hydrochloride has been shown to increase plasma thioridazine levels.
- Pimozide: Paroxetine hydrochloride has been shown to increase plasma pimozide levels. Elevation of pimozide blood concentration may result in QT interval prolongation and severe arrhythmias including torsade de pointes.
See 2 CONTRAINDICATIONS and 9.4 Drug-Drug Interactions
Table 5 – Established or Potential Drug-Drug Interactions
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| MAOIs including linezolid and methylthioninium chloride (methylene blue) | C | Reports include serious, sometimes fatal, reactions including hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes that include extreme agitation progressing to delirium and coma. Some cases showed features of serotonin syndrome or neuroleptic malignant syndrome (see 7 WARNINGSAND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome). | Concurrent use of MAOIs and MAR-PAROXETINE is contraindicated (see 2 CONTRAINDICATIONS, 9.1 Serious Drug Interactions). MAR-PAROXETINE should not be used in combination with MAOIs or within a minimum of 2 weeks of terminating treatment with MAOIs. Treatment with MAR-PAROXETINE should then be initiated cautiously and dosage increased gradually until optimal response is reached. MAOIs should not be introduced within 2 weeks of cessation of therapy with MAR-PAROXETINE. |
| Thioridazine | T | Possible increase in thioridazine plasma levels due to PK interaction via CYP2D6 based on in vivo studies. Therefore, possible increased risk of QT prolongation, which is associated with serious ventricular arrhythmias, such as torsade de pointes-type arrhythmias, and sudden death. | MAR-PAROXETINE should not be used in combination with thioridazine or within a minimum of 2 weeks of terminating treatment with paroxetine (see 2 CONTRAINDICATIONS, 9.1 Serious Drug Interactions). |
| Pimozide | CT | Increased systemic exposure to pimozide due to PK interaction likely via CYP2D6. Therefore, possible increased risk of QT prolongation, which is associated with serious ventricular arrhythmias, such as torsade de pointes-type arrhythmias, and sudden death. | In an open label study of healthy volunteers, co-administration of a single dose of 2 mg pimozide, under steady state conditions of paroxetine hydrochloride (titrated to 60 mg daily) was associated with mean increases in pimozide AUC of 151% and Cmax of 62%, compared to pimozide administered alone. Concomitant use of MAR-PAROXETINE and pimozide is contraindicated and paroxetine should not be started until a minimum of 2 weeks after pimozide has been discontinued (see 2 CONTRAINDICATIONS, 9.1 Serious Drug Interactions). |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Antipsychotic drugs | C | Possible increased risk of neuroleptic malignant syndrome (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome). | MAR-PAROXETINE should be used with caution in patients already receiving antipsychotics/ neuroleptics. |
| Serotonergic drugs such as tryptophan, triptans, serotonin reuptake inhibitors, lithium, fentanyl and its anologues, dextromethorphan, tramadol, tapentadol, meperidine, methadone and pentazocine or St. John's Wort | T | Potential increased risk of serotonin syndrome and neuroleptic malignant syndrome (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome). | Caution is advised. Based on the mechanism of action of paroxetine and the potential for serotonin syndrome. |
Drugs affecting platelet function (e.g. NSAIDs, ASA and other anticoagulants) | E | Serotonin release by platelets plays an important role in hemostasis. Interference with serotonin reuptake and the occurrence of upper gastrointestinal bleeding may be potentiated by the use of NSAIDs, ASAs or other anticoagulants. Altered anticoagulant effects, including increased bleeding, have been reported when SSRIs are co-administered with warfarin. | Based on case-control and epidemiological cohort studies. Patients receiving warfarin therapy should be carefully monitored when MAR-PAROXETINE is initiated or discontinued (see 7 WARNINGS AND PRECAUTIONS, Abnormal Bleeding). |
| Lithium | T | Potential increased risk of serotonin syndrome. | In a clinical study, no pharmacokinetic interaction between paroxetine and lithium was observed. However, due to the potential for serotonin syndrome, caution is advised when MAR-PAROXETINE is co-administered with lithium. |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Triptans | C | Weakness, hyperreflexia, incoordination seen after use of SSRI and triptan (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome). | Based on rare postmarketing reports. If concomitant treatment with triptan and an SSRI (e.g. fluoxetine, fluvoxamine, paroxetine, sertraline) is clinically warranted, appropriate observation of the patient is advised. |
| Tryptophan | T | Use of paroxetine hydrochloride and tryptophan may result in headache, nausea, sweating and dizziness, as well as serotonin syndrome (see 7 WARNINGS AND PRECAUTIONS, Serotonin Toxicity/Neuroleptic Malignant Syndrome). | Tryptophan may be metabolised to serotonin. Concomitant use of MAR-PAROXETINE and tryptophan is not recommended. |
| Tamoxifen | CT | Reduced plasma concentrations and possible efficacy of endoxifen, the active metabolite of tamoxifen (see 7 WARNINGS AND PRECAUTIONS, Potential for reduced efficacy of Tamoxifen with concomitant SSRI use, including Paroxetine hydrochloride ). | Tamoxifen is metabolised into endoxifen via CYP2D6. Paroxetine inhibits CYP2D6 thereby reducing endoxifen plasma levels. |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Drugs metabolised by CYP2D6 | CT | Possible altered systemic exposure of CYP2D6-metabolised drugs due to inhibition of CYP2D6 by paroxetine. | In two studies, daily dosing of paroxetine hydrochloride (20 mg qd) under steady state conditions increased the following mean pharmacokinetic parameters for a single (100 mg) dose of desipramine in extensive metabolizers: Cmax (2 fold), AUC (6 fold), and T½ (3-5 fold). Concomitant steady-state paroxetine hydrochloride treatment did not result in any further impairment of desipramine elimination in poor metabolizers. Insufficient information is available to provide recommendations on the necessary dosage adjustments for tricyclic antidepressants or paroxetine hydrochloride, if these drugs are to be used in combination. Plasma tricyclic antidepressant concentrations may need to be monitored in such instances. Concomitant use of paroxetine hydrochloride with other drugs metabolized by CYP2D6 has not been formally studied but may require lower doses than usually prescribed for either paroxetine hydrochloride or the other drug. Drugs metabolized by CYP2D6 include certain tricyclic antidepressants (e.g. nortriptyline, amitriptyline, imipramine and desipramine), selective serotonin reuptake inhibitors (e.g. fluoxetine), phenothiazine neuroleptics (e.g. perphenazine), risperidone, atomoxetine, Type IC antiarrhythmics (e.g. propafenone and flecainide), and metoprolol. |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Drugs metabolised by CYP3A4 | T | No expected effect of paroxetine on CYP3A4-metabolised drugs. | An in vivo interaction study involving the co-administration under steady state conditions of paroxetine hydrochloride and terfenadine, a substrate for CYP3A4, revealed no effect of paroxetine hydrochloride on terfenadine pharmacokinetics. In addition, in vitro studies have shown ketoconazole, a potent inhibitor of CYP3A4 activity, to be at least 100 times more potent than paroxetine as an inhibitor of the metabolism of several substrates for this enzyme, including terfenadine, astemizole, cisapride, triazolam and cyclosporin. Based on the assumption that the relationship between paroxetine’s in vitro Ki and its lack of effect on terfenadine’s in vivo clearance predicts its effect on other CYP3A4 substrates, paroxetine’s extent of inhibition of CYP3A4 activity would not be expected to be of clinical significance. |
| Neuromuscular blockers | C | Some antidepressants including paroxetine may reduce plasma cholinesterase activity resulting in a prolongation of the neuromuscular blocking action of succinylcholine. | Based on in vitro studies as well as a small number of clinical reports |
| Microsomal enzyme inhibition/induction | T | Altered systemic exposure to paroxetine. | The metabolism and pharmacokinetics of paroxetine hydrochloride may be affected by the induction or inhibition of drug metabolizing enzymes. |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Drugs highly bound to plasma protein | T | Administration of paroxetine hydrochloride to a patient taking another drug that is highly protein bound may cause increased free concentrations of the other drug, potentially resulting in adverse events. Conversely, adverse effects could result from displacement of paroxetine by other highly bound drugs. | Paroxetine is highly bound to plasma protein. |
| Anti-cholinergic drugs | CT | Paroxetine hydrochloride has been reported to increase significantly the systemic bioavailability of procyclidine. Steady state plasma levels of procyclidine (5 mg daily) were elevated by about 40% when 30 mg paroxetine was co- administered to steady-state. | If anti-cholinergic effects are seen, the dose of procyclidine should be reduced. |
| Antiretroviral | CT | Co-administration of fosamprenavir/ritonavir with paroxetine significantly decreased plasma levels of paroxetine (by ~ 60% in one study). | Any dose adjustment should be guided by clinical effect (tolerability and efficacy). |
| Phenobarbital | CT | Chronic daily dosing with phenobarbital (100 mg qid for 14 days) decreased the systemic availability of a single 30 mg dose of paroxetine in some subjects. The AUC and T½ of MAR-PAROXETINE were reduced by an average of 25 and 38% respectively compared to paroxetine hydrochloride administered alone. The effect of paroxetine hydrochloride on phenobarbital pharmacokinetics was not studied. | No initial MAR-PAROXETINE dosage adjustment is considered necessary when co-administered with phenobarbital; any subsequent adjustment should be guided by clinical effect. |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Anti-convulsants | CT | The co-administration of paroxetine hydrochloride (30 mg/day for 10 days) had no significant effect on the plasma concentrations of patients with epilepsy on long-term treatment with carbamazepine (600-900 mg/day) n=6, phenytoin (250-400 mg/day) n=6 and sodium valproate (300-2500 mg/day) n=8. In healthy volunteers, co- administration of paroxetine with phenytoin has been associated with decreased plasma levels of paroxetine and an increased incidence of adverse experiences. Co-administration of paroxetine hydrochloride with anticonvulsants may be associated with an increased incidence of adverse experiences. | No initial dosage adjustment of MAR-PAROXETINE is considered necessary when the drug is to be co- administered with known drug metabolizing enzyme inducers (e.g. carbamazepine, phenytoin, sodium valproate) and any subsequent dosage adjustment should be guided by clinical effect. |
| CNS drugs | CT | Experience in a limited number of healthy subjects has shown that paroxetine hydrochloride does not increase the sedation and drowsiness associated with haloperidol, amylbarbitone or oxazepam, when given in combination. | Since the effects of concomitant administration of paroxetine hydrochloride with neuroleptics have not been studied, the use of MAR-PAROXETINE with these drugs should be approached with caution. |
| Diazepam | CT | A multiple dose study of the interaction between paroxetine hydrochloride and diazepam showed no alteration in the pharmacokinetics of paroxetine hydrochloride that would warrant changes in the dose of paroxetine hydrochloride for patients receiving both drugs. The effects of paroxetine hydrochloride on the pharmacokinetics of diazepam were not evaluated. | |
| Cardiovascular drugs | CT | Multiple dose treatment with paroxetine hydrochloride 30 mg/day has little or no effect on the steady-state pharmacokinetics of digoxin (0.25 mg qd) or propanolol (80 mg bid). |
| Paroxetine Hydrochloride | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Theophylline | C | Reports of elevated theophylline levels associated with paroxetine hydrochloride treatment have been reported. | While this interaction has not been formally studied, it is recommended that theophylline levels be monitored when these drugs are concurrently administered. |
| Cimetidine | CT | Steady state levels of paroxetine hydrochloride (30 mg daily) were elevated by about 50% when cimetidine (300 mg tid), a known drug metabolizing enzyme inhibitor, was co- administered to steady-state. | Consideration should be given to using doses of MAR-PAROXETINE towards the lower end of the range when co- administered with known drug metabolizing enzyme inhibitors. |
Legend: C = Case Study; CT = Clinical Trial; E = Epidemiological Study; T = Theoretical
9.5 Drug-Food Interactions
The absorption and pharmacokinetics of paroxetine hydrochloride are not affected by food or antacids.
9.6 Drug-Herb Interactions
St. John’s Wort: In common with other SSRIs, pharmacodynamic interactions between paroxetine and the herbal remedy St. John’s Wort may occur and may result in an increase in undesirable effects.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Paroxetine is a potent and selective serotonin (5-hydroxytryptamine, 5-HT) reuptake inhibitor (SSRI). This activity of the drug on brain neurons is thought to be responsible for its antidepressant and anxiolytic action in the treatment of depression, obsessive-compulsive disorder (OCD), panic disorder, social phobia (social anxiety disorder), generalized anxiety disorder (GAD) and posttraumatic stress disorder (PTSD).
Paroxetine is a phenylpiperidine derivative which is chemically unrelated to the tricyclic or tetracyclic antidepressants. In receptor binding studies, paroxetine did not exhibit significant affinity for the adrenergic (α1, α2, β), dopaminergic, serotonergic (5HT1, 5HT2), or histaminergic receptors of rat brain membrane. A weak affinity for the muscarinic acetylcholine receptor was evident. The predominant metabolites of paroxetine are essentially inactive as 5-HT reuptake inhibitors.
10.2 Pharmacodynamics
Paroxetine 30 mg administered in single doses to healthy non-depressed volunteers did not impair psychomotor function which was measured by psychomotor tasks such as Morse tapping and motor manipulation, assessment of subjective perception and general assessment of arousal.
Paroxetine at doses of up to 40 mg daily produces no clinically significant changes in blood pressure, heart rate or ECG after administration to healthy subjects.
10.3 Pharmacokinetics
No clear dose relationship has been demonstrated for the antidepressant effects of paroxetine at doses above 20 mg/day. The results of fixed-dose studies comparing paroxetine and placebo in the treatment of depression, panic disorder, generalized anxiety disorder and posttraumatic stress disorder revealed a dose dependency for some adverse events.
Absorption
Paroxetine is well absorbed after oral administration. In healthy volunteers, the absorption of a single 30 mg oral dose of paroxetine was not appreciably affected by the presence or absence of food.
Both the rate of absorption and the terminal elimination half-life appear to be independent of dose. Steady-state plasma concentrations of paroxetine are generally achieved in 7 to 14 days. No correlation has been established between paroxetine plasma concentrations and therapeutic efficacy or the incidence of adverse reactions.
In healthy young volunteers receiving a 20 mg daily dose of paroxetine for 15 days, the mean maximal plasma concentration was 41 ng/mL at steady state (see Table 6). Peak plasma levels generally occurred within 3 to 7 hours.
Distribution
Owing to the extensive distribution of paroxetine into the tissues, less than 1% of the total drug in the body is believed to reside in the systemic circulation. At therapeutic concentrations, the plasma protein binding of paroxetine is approximately 95%.
Metabolism
Paroxetine is subject to a biphasic process of metabolic elimination which involves presystemic (first- pass) and systemic pathways. First-pass metabolism is extensive, but maybe partially saturable, accounting for the increased bioavailability observed with multiple dosing. The metabolism of paroxetine is accomplished in part by cytochrome P450 (2D6). Saturation of this enzyme at clinical doses appears to account for the nonlinearity of paroxetine kinetics with increasing dose and increasing duration of treatment. The role of this enzyme in paroxetine metabolism also suggests potential drug- drug interactions (see 9 DRUG INTERACTIONS). The majority of the dose appears to be oxidized to a catechol intermediate which is converted to highly polar glucuronide and sulphate metabolites through methylation and conjugation reactions. The glucuronide and sulphate conjugates of paroxetine are about > 10,000 and 3,000 times less potent, respectively, than the parent compound as inhibitors of 5- HT reuptake in rat brain synaptosomes.
Elimination
Following the single or multiple dose administration of paroxetine at doses of 20 to 50 mg, the mean elimination half-life value for healthy subjects appears to be about 24 hours, although a range of 3 to 65 hours has been reported.
Approximately 64% of an administered dose of paroxetine is eliminated by the kidneys and 36% in the feces. Less than 2% of the dose is recovered in the form of the parent compound.
Special Populations and Conditions
- Geriatrics: In elderly subjects, increased steady-state plasma concentrations and prolongation of the elimination half-life were observed relative to younger adult controls (see Table 6). Elderly patients should, therefore, be initiated and maintained at the lowest daily dosage of paroxetine which is associated with clinical efficacy (see 4.2 Recommended Dose and Dosage Adjustment).
- Hepatic Insufficiency: The results from a multiple dose pharmacokinetic study in subjects with severe hepatic dysfunction suggest that the clearance of paroxetine is markedly reduced in this patient group (see Table 6). As the elimination of paroxetine is dependent upon extensive hepatic metabolism, its use in patients with hepatic impairment should be undertaken with caution (see 4.2 Recommended Dose and Dosage Adjustment).
- Renal Insufficiency: In a single dose pharmacokinetic study in patients with mild to severe renal impairment, plasma levels of paroxetine tended to increase with deteriorating renal function (see Table 7). As multiple-dose pharmacokinetic studies have not been performed in patients with renal disease, paroxetine should be used with caution in such patients (see 4.2 Recommended Dose and Dosage Adjustment).
Table 6 Steady state pharmacokinetics of paroxetine after doses of 20 mg daily (mean and range)
Young Healthy Subjects [n=22] | Elderly Healthy Subjects [n=22] | Hepatically* Impaired Subjects [n=10] | |
|---|---|---|---|
| Cmax (ss) (ng/mL) | 41 (12-90) | 87 (18-154) | 87 (11-147) |
| Tmax (ss) (hours) | 5.0 (3-7) | 5.0 (1-10) | 6.4 (2-11) |
| Cmin (ss) (ng/mL) | 21 (4-51) | 58 (9-127) | 66 (7-128) |
| AUC (ss) (ng·h/mL) | 660 (179-1436) | 1580 (221-3286) | 1720 (194-3283) |
| T½ (hour) | 19 (8-43) | 31 (13-92) | 66 (17-152) |
*Galactose elimination capacity 30-70% of normal.
A wide range of inter individual variation is observed for the pharmacokinetic parameters.
Table 7 Pharmacokinetics of paroxetine after a single 30 mg dose in normal subjects and those with renal impairment
aRenally Impaired Subjects Severe [n=6] | bRenally Impaired Subjects Moderate [n=6] | cHealthy young subjects [n=6] | |
|---|---|---|---|
| Cmax (ng/mL) | 46.2 (35.9-56.7) | 36 (3.6-59.4) | 19.8 (1.4-54.8) |
| Tmax (hour) | 6.5 (4.0-11.0) | 4.8 (1.5-9.0) | 4.3 (1-7) |
| AUC4 (ng·h/mL) | 2046 (605-3695) | 1053 (48-2087) | 574 (21-2196) |
| T½ (hour) | 29.7 (10.9-54.8) | 18.3 (11.2-32.0) | 17.3 (9.6-25.1) |
a Creatinine clearance = 13-27 mL/min b Creatinine clearance = 32-46 mL/min c Creatinine clearance > 100 mL/min Abbreviations:
Cmax = maximum plasma concentration; Tmax = time to reach Cmax
AUC4 = Area under the plasma concentration time curve at infinity T½ = terminal elimination half-life
11 STORAGE, STABILITY AND DISPOSAL
Store at 15 to 30 ° C.
12 SPECIAL HANDLING INSTRUCTIONS
No Special Handling Instructions are required for this drug product.
PART II: SCIENTIFIC INFORMATION
- 13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Paroxetine hydrochloride
Chemical name: (3S-trans)-3-[(1,3-Benzodioxol-5-yloxy)methyl]-4-(4-fluorophenyl) piperidine hydrochloride hemihydrate
Molecular formula and molecular mass: C19H21ClFNO3. ½ H2O
374.8 g/mol (as hemihydrate salt)
Structural formula:
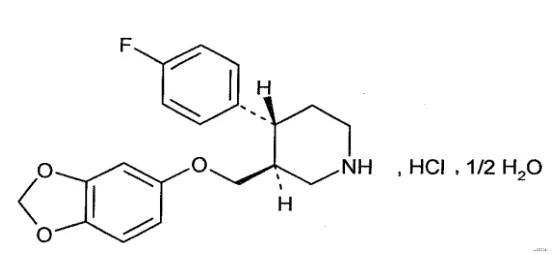
Physicochemical properties:
Description: a white to almost white crystalline powder
Melting point: 140oC – 147oC
pH Values: 5.0 to 6.0
Specific optical: -86o to -91o
rotation
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication Major Depressive Disorder
The efficacy of paroxetine hydrochloride as a treatment for depression has been established in six placebo-controlled clinical trials of 6 weeks in duration performed in patients with depression (ages 18 to 73).
In these 6 studies, paroxetine hydrochloride was shown to be significantly more effective than placebo in treating depression according to the following measures: Hamilton Depression Rating Scale (HDRS), the Hamilton depressed mood item, and the Clinical Global Impression (CGI) – Severity of Illness.
A study of outpatients with recurrent major depressive disorder who had responded to paroxetine hydrochloride (HDRS total score < 8) during an initial 8-week open-treatment phase and were then randomized to continuation on paroxetine hydrochloride or placebo for 1 year demonstrated that a significantly lower proportion of patients treated with paroxetine hydrochloride (15%) compared to placebo (39%) met criteria for partial relapse1. Criteria for full relapse2 were met by a significantly lower percentage of paroxetine hydrochloride treated patients (12%) compared to placebo treated patients (28%). Effectiveness was similar for male and female patients.
1 Partial relapse was characterized by requirement for additional antidepressant medication and fulfillment of DSM IIIR criteria for major depressive episode.
2 Full relapse was characterized by requirement for additional antidepressant treatment, fulfillment of DSM IIIR criteria for major depressive episode, deterioration in depressive symptoms for at least 1 week, increase in CGI-Severity of Illness score by ≥ 2 points and CGI-Severity of Illness score of ≥4 (least moderately ill).
Obsessive-Compulsive Disorder
Three double-blind, placebo-controlled clinical trials of 12 weeks in duration have been performed to investigate the efficacy of paroxetine hydrochloride in obsessive-compulsive disorder: two flexible dose studies (20 to 60 mg/day) and one fixed dose study (20, 40, & 60 mg/day).
Results for the fixed dose study and one of the flexible dose studies showed statistically significant differences from placebo in favour of paroxetine hydrochloride in terms of mean change from baseline to endpoint on the Yale-Brown Obsessive-Compulsive Scale and/or the National Institute of Mental Health Obsessive- Compulsive Scale. In the fixed dose study, the proportion of patients who were considered to be much or very much improved at endpoint according to a Clinical Global Impression of improvement was 15% (13/88) in the placebo group, 20% (17/85) in the 20 mg/day group, 36% (30/83) in the 40 mg/day group, and 37% (31/83) in the 60 mg/day group. In the two flexible dose studies, placebo response rates according to this criterion were 28% (28/99) and 25% (19/75), while paroxetine hydrochloride response rates were 45% (89/198) and 35% (28/79), respectively.
Panic Disorder (with or without agoraphobia)
One fixed dose and three flexible dose placebo-controlled clinical trials of 10 to 12 weeks in duration have been performed to investigate the efficacy of paroxetine hydrochloride in panic disorder.
The fixed dose study and two of the three flexible dose studies were supportive of differences from placebo in favour of paroxetine hydrochloride for measures of panic attack frequency. At endpoint, in the fixed dose study, the proportion of patients who were free of panic attacks was 44% (29/66) for the placebo group, 56% (33/59) for the 10 mg/day paroxetine hydrochloride group, 57% (35/61) for the 20 mg/day paroxetine hydrochloride group, and 76% (47/62) for the 40 mg/day paroxetine hydrochloride group.
Social Phobia (Social Anxiety Disorder)
One fixed dose and two flexible dose placebo-controlled clinical trials of 12 weeks in duration have been performed to investigate the efficacy of paroxetine hydrochloride in social phobia (social anxiety disorder).
These studies showed statistically significant differences from placebo in favour of paroxetine hydrochloride in terms of mean change from baseline to endpoint on the Liebowitz Social Anxiety Scale and the percentage of therapeutic responders according to the Clinical Global Impression of Improvement. In the fixed dose study, the proportion of patients who were considered to be much or very much improved at week 12 of treatment according to the Clinical Global Impression of Improvement was 28.3% (26/92) in the placebo group, 44.9% (40/89) in the 20 mg/day group, 46.6% (41/88) in the 40 mg/day group, and 42.9% (39/91) in the 60 mg/day group. In the two flexible dose (20-50 mg/day) studies, placebo response rates according to this criterion were 23.9% (22/92) and 32.4% (47/145), while paroxetine hydrochloride response rates were 54.9% (50/91) and 65.7% (90/137), respectively.
Generalized Anxiety Disorder (GAD)
The effectiveness of paroxetine hydrochloride in the treatment of Generalized Anxiety Disorder (GAD) (DSM IV) was demonstrated in two 8-week, multicentre, placebo-controlled studies. One trial was a flexible dose (20 to 50 mg/day) study while the other was a multiple fixed dose (20 or 40 mg/day) study.
In both studies paroxetine hydrochloride demonstrated statistically significant superiority over placebo on the primary outcome measure - the Hamilton Rating Scale for Anxiety (HAM-A) total score, and on a number of secondary outcomes including the HAM-A anxiety and tension items, the Clinical Global Impression (CGI) responder criterion and the Sheehan Disability Scale (SDS). An additional 8-week flexible dose study did not demonstrate a significant difference between paroxetine hydrochloride (20 to 50 mg/day), and placebo on the primary outcome measure. However, paroxetine hydrochloride (20 to 50 mg/day) was more effective than placebo on many secondary study outcomes.
Posttraumatic Stress Disorder (PTSD)
The efficacy of paroxetine hydrochloride in the treatment of Posttraumatic Stress Disorder (PTSD) was demonstrated in two 12 week, multicentre placebo controlled studies (Study 1 and Study 2) in adult patients who met the DSM-IV criteria for PTSD. Study outcome was assessed by (i) the Clinician Administered PTSD Scale
Part (CAPS-2) score and (ii) the Clinical Global Impression Global Improvement Item (CGI-I). The CAPS-2 is a multi-item instrument that measures the three PTSD diagnostic symptom clusters of: re-experiencing/intrusion, avoidance/numbing and hyperarousal.
Study 1 was a 12-week study comparing fixed paroxetine doses of 20 or 40 mg/day to placebo. Study 2 was a 12-week flexible-dose study comparing paroxetine (20 to 50 mg daily) to placebo.
The two primary outcomes for each trial were (i) change from baseline to endpoint on the CAPS-2 total score (17 items), and (ii) proportion of responders on the CGI-I, where responders were defined as patients having a score of 1 (very much improved) or 2 (much improved).
In study 1, paroxetine hydrochloride 20 mg and 40 mg were demonstrated to be significantly superior to placebo for the CAPS-2 total score, and on proportion of responders on the CGI-I.
In study 2, paroxetine hydrochloride was demonstrated to be significantly superior to placebo for the CAPS-2 total scorer, and on proportion of responders on the CGI-I.
The majority (66-68%) of patients in these trials were women. Subgroup analyses did not indicate differences in treatment outcomes as a function of gender. There were an insufficient number of patients who were 65 years or older or were non-Caucasian to conduct subgroup analyses on the basis of age or race, respectively.
14.2 Comparative Bioavailability Studies
A randomized, two-treatment, two-period, single oral dose (1 x 30 mg), crossover comparative bioavailability study of MAR-PAROXETINE tablets, 30 mg (Marcan Pharmaceuticals Inc.) and PAXIL® tablets, 30 mg (GlaxoSmithKline Inc.), was conducted in healthy, adult male subjects under fasting conditions. Comparative bioavailability data from 28 subjects that were included in the statistical analysis are presented in the following tables:
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Paroxetine (1 x 30 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 136.76 198.84 (87.38) | 146.66 215.72 (88.36) | 93.3 | 85.0 – 102.3 |
AUCI (ng·h/mL) | 153.63 243.88 (115.95) | 162.32 249.58 (102.49) | 94.6 | 86.8 – 103.3 |
Cmax (ng/mL) | 7.12 8.60 (60.00) | 7.70 9.37 (57.13) | 92.4 | 85.5 – 99.9 |
Tmax3 (h) | 6.00 (5.00-7.00) | 6.33 (5.00-7.50) | ||
T½4 (h) | 17.05 (75.57) | 15.44 (48.92) | ||
1 MAR-PAROXETINE (paroxetine as paroxetine hydrochloride hemihydrate) tablets, 30 mg (Marcan Pharmaceuticals Inc.)
2 PAXIL® (paroxetine as paroxetine hydrochloride) tablets, 30 mg (GlaxoSmithKline Inc., Canada)
3 Expressed as the median (range) only
4 Expressed as the arithmetic mean (CV %) only
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
Animal Pharmacology
In vitro: Paroxetine showed a high potency for the inhibition of 5-HT reuptake in rat hypothalamic synaptosomes (Ki=1.1nM), but exerted relatively weak effects upon noradrenaline reuptake (Ki=350nM). The predominant metabolites of paroxetine, a sulphate and a glucuronide conjugate, were essentially inactive as 5-HT reuptake inhibitors. Paroxetine has a low affinity for muscarinic cholinergic receptors (Ki of 89 nM for displacement of [3H] quinuclidinyl benzilate). Animal studies have indicated only weak anticholinergic properties.
Radioligand binding techniques in rat brain, in vitro, have indicated that paroxetine has little affinity for α1, α2 and β-adrenoceptors, dopamine (D2), 5-HT1-like, 5-HT2 and histamine (H1) receptors at concentrations below 1 μM. This lack of interaction with post-synaptic receptors in vitro is substantiated by in vivo studies which demonstrate a lack of CNS depressant and hypotensive properties.
In vivo: In mice, paroxetine (ED50=0.4 mg/kg p.o.) was associated with potent and prolonged potentiation of the hypermotility induced by the 5-HT precursor, 5-hydroxytryptophan. Similarly, the anticonvulsant effects of 5-hydroxytryptophan in a mouse electroshock model were potentiated by paroxetine (ED50=0.4 mg/kg p.o.). In rats, paroxetine (ED50=0.8 mg/kg p.o.) inhibited the hypermotility induced by p-chloroamphetamine, an agent which depletes neuronal 5-HT stores. Paroxetine, 1 mg/kg i.p., in conscious rats with chronically implanted cortical electrodes, produced essentially no changes in the power spectrum and frequency analysis of the EEG.
Electrophysiological measures have demonstrated that paroxetine has a vigilance-increasing activity in animals. Oral doses of paroxetine 0.32 to 18 mg/kg to rats lengthened the waking period and shortened the slow-wave and paradoxical sleep periods in a dose-dependent fashion. As with other selective 5-HT uptake inhibitors, paroxetine, at a dose of 5 mg/kg i.p., causes symptoms of excessive 5-HT receptor stimulation when administered to rats previously given monoamine oxidase (MAO) inhibitors such as tranylcypromine or phenelzine, or the 5-HT precursor L-tryptophan.
Behavioural and EEG studies indicate that paroxetine is weakly activating at doses above those generally required to inhibit 5-HT reuptake. The activating properties are not "amphetamine-like" in nature. In rats trained to discriminate d-amphetamine, 1 mg/kg i.p., from saline, no generalization to amphetamine was observed after administration of paroxetine (0.3, 1, 3 or 10 mg/kg i.p.). Paroxetine caused seizures in mice at a lethal dose of 300 mg/kg p.o. At a dose of 50 mg/kg p.o., paroxetine lowered the threshold for electroshock-induced seizures in mice.
Animal studies indicate that paroxetine is well tolerated by the cardiovascular system. When the cardiovascular effects of paroxetine and amitriptyline were compared in the conscious rabbit and anaesthetized cat, intravenous doses of paroxetine approximately 2 to 4 times higher (on a mg/kg basis) than those of amitriptyline were required to produce significant changes in blood pressure, heart rate and electrocardiographic parameters. Similarly, in the pentobarbital anaesthetized dog, i.v. imipramine, amitriptyline and clomipramine (in doses of 10 mg/kg) caused severe atrioventricular block and ventricular arrhythmia’s, while equivalent doses of paroxetine resulted in only slight prolongation of the PQ interval. In addition, low doses (0.3 to 1 mg/kg) of the tricyclic antidepressants caused marked tachycardia, whereas paroxetine in doses up to 10 mg/kg had no effect on heart rate.
Studies in the spontaneous hypertensive rat indicate that, in contrast to antidepressants which inhibit the uptake of noradrenaline, paroxetine at 5 mg/kg i.v. has a much reduced propensity to inhibit the antihypertensive effects of guanethidine.
5-HT is transported into blood platelets and central neurons by a similar active uptake transporter mechanism in the cell membrane. Thus, in common with other selective 5-HT reuptake inhibitors, administration of paroxetine results in depletion of 5-HT from platelets. This has been reported after repeated daily administration of paroxetine at doses of 0.1, 1 and 10 mg/kg i.p. in mice and rats, 1 to 7.5 mg/kg p.o. in monkeys and 10-50 mg orally to healthy human volunteers. Similarly, whole blood 5- HT levels were shown to be depleted in depressed patients after paroxetine administration.
General Toxicology
General toxicity studies have been conducted in rhesus monkeys and rats, in both of which the metabolic pathway for paroxetine is the same as in man.
- Acute Toxicity: In relation to the clinical dose, the acute LD50 of paroxetine is very high in both mice and rats (approximately 350 mg/kg).
Long-Term Toxicity: The no-toxic effect levels in the rhesus monkeys and rats were 4 to 10 times and 6 to 15 times the recommended range of clinical doses respectively. At higher doses (40 mg/kg for 3 months and 25 mg/kg for 12 months), lipidosis was observed in several tissues of rats (lungs, mesenteric lymph nodes, epididymides, retinal tissues - the latter by electron microscopy only). As paroxetine is a lipophilic amine with both hydrophobic and hydrophilic moieties, it may accumulate in lysosomes leading to an impairment of lipid catabolism and, hence, the accumulation of lipids within the lysosomes. It should be
- noted that the slight degree of lipidosis seen in the rat was restricted to doses and plasma levels much higher than those observed in man. In a clinical study investigating lamellated inclusion bodies in peripheral white blood cells during long-term therapy, no difference between placebo and paroxetine could be detected.
Carcinogenicity
No carcinogenic potential was detected in rat (dose levels of 1, 5 and 20 mg/kg/day) and mouse (dose levels of 1, 5 and 25 mg/kg/day) life-span studies. A non dose-related increase in malignant liver cell tumours occurred in male mice at 1 and 5 mg/kg/day which was statistically significant at 5 mg/kg/day. There was no increase at 25 mg/kg/day or in female mice and the incidence was within the historical control range.
Reproductive and Developmental Toxicology
5-Hydroxytryptamine and compounds modulating this amine are known to affect reproductive function in animals and at high dose levels cause marked overt toxicity. Paroxetine at 15 and 50 mg/kg (hydrochloride salt) has been shown to impair reproductive function in rats.
In male rats, chronic administration of a 50 mg/kg dose has been associated with granulomatous reactions in the epididymides accompanied by atrophy and degeneration of the seminiferous tubules. There were no biologically significant effects on fertility of female rats but corpora lutea count was slightly reduced and preimplantation loss slightly increased at 50 mg/kg in association with marked maternal toxicity.
Reproduction studies were performed in rats and rabbits at doses up to 42 and 5 times the maximum recommended daily human dose (60 mg) on a mg/kg basis. These are 8.3 (rat) and 1.7 (rabbit) times the maximum recommended human dose on a mg/m2 basis. These studies have revealed no evidence of teratogenic effects or of selective toxicity to the embryo.
Special Toxicology
- Immunotoxicity
Specific studies have demonstrated that paroxetine is unlikely to possess the potential for immunotoxicity.
Serum samples were obtained from depressed patients who had received 30 mg of paroxetine daily for between six and twelve months, from groups of rats on a repeat dose toxicity study in which daily doses of 1, 5 and 25 mg/kg of paroxetine were administered for 52 weeks, from guinea pigs epicutaneously exposed (topically under an occlusive patch) to paroxetine and from New Zealand White (NZW) rabbits parenterally(i.m. and s.c.) injected with paroxetine in Freund's adjuvant. In addition, as a positive control, sera were obtained from NZW rabbits which had been immunized by and s.c. injections of Freund's adjuvant emulsions containing paroxetine chemically conjugated to bovine gamma globulin (BGG).
Serum antibody levels were assessed by enzyme- or radio-immunoassays (ELISA or RIA). No anti- paroxetine antibody activity was detected in serum samples from patients, from rats in the toxicity study, from guinea pigs epicutaneously exposed to paroxetine, or from rabbits parenterally injected with paroxetine. Serum anti-paroxetine antibody was detected in rabbits immunized with Freund's adjuvant emulsions containing paroxetine coupled with BGG, verifying that the RIA system employed was capable of detecting antibodies directed against paroxetine.
Paroxetine also did not induce contact sensitivity reactions in guinea pigs following epicutaneous exposure.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1.
PAXIL® (paroxetine hydrochloride) Tablets, 10 mg, 20 mg and 30 mg, Submission Control No.: 263621,
Product Monograph, GlaxoSmithKline Inc., Date of Revision: SEP 22, 2022.