


Product Monograph - Minoxidil 5% Men / Hommes
RECENT MAJOR LABEL CHANGES
4 DOSAGE AND ADMINISTRATION 4.1 Dosing Considerations | 2026-07 |
|---|---|
| 5 OVERDOSAGE | 2026-07 |
7.1 Special Populations, 7.1.2 Breast-feeding, 7.1.3 Pediatrics | 2026-07 |
| 8 ADVERSE REACTIONS, 8.5 Post-Market Adverse Reactions | 2026-07 |
| 17 SUPPORTING PRODUCT MONOGRAPHS | 2026-07 |
TABLE OF CONTENTS
TABLE OF CONTENTS .............................................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ............................................................................... 4
1 INDICATIONS ..................................................................................................................................... 4
1.1 Pediatrics .............................................................................................................................................. 4
1.2 Geriatrics ............................................................................................................................................... 4
2 CONTRAINDICATIONS ..................................................................................................................... 4
4 DOSAGE AND ADMINISTRATION ................................................................................................... 5
4.1 Dosing Considerations ........................................................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ............................................................................... 5
4.4 Administration....................................................................................................................................... 5
4.5 Missed Dose ......................................................................................................................................... 5
5 OVERDOSAGE .................................................................................................................................. 6
6 DOSAGE FORM, STRENGTH, COMPOSITION AND PACKAGING ................................................ 7
7 WARNINGS AND PRECAUTIONS .................................................................................................... 7
7.1 Special Populations ............................................................................................................................. 8
7.1.1 Pregnant Women ............................................................................................................................. 8
7.1.2 Breast-feeding................................................................................................................................... 8
7.1.3 Pediatrics ........................................................................................................................................... 8
7.1.4 Geriatrics ........................................................................................................................................... 8
8 ADVERSE REACTIONS .................................................................................................................... 9
8.1 Adverse Reaction Overview ............................................................................................................... 9
8.2 Clinical Trial Adverse Reactions...................................................................................................... 10
8.3 Less Common Clinical Trial Adverse Reactions ........................................................................... 13
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data .......................................................................................................................................................... 13
8.5 Post-Market Adverse Reactions ...................................................................................................... 13
9 DRUG INTERACTIONS ................................................................................................................... 15
9.2 Drug Interactions Overview .............................................................................................................. 15
9.3 Drug-Behavioural Interactions ......................................................................................................... 15
9.4 Drug-Drug Interactions ..................................................................................................................... 15
9.5 Drug-Food Interactions ..................................................................................................................... 15
9.6 Drug-Herb Interactions ..................................................................................................................... 15
9.7 Drug-Laboratory Test Interactions .................................................................................................. 16
10 CLINICAL PHARMACOLOGY ....................................................................................................... 17
10.1 Mechanism of Action ....................................................................................................................... 17
10.2 Pharmacodynamics ......................................................................................................................... 17
10.3 Pharmacokinetics ............................................................................................................................. 18
11 STORAGE, STABILITY AND DISPOSAL ..................................................................................... 22
PART II: SCIENTIFIC INFORMATION ..................................................................................................... 23
13 PHARMACEUTICAL INFORMATION ............................................................................................ 23
14 CLINICAL TRIALS ......................................................................................................................... 23
14.1 Trial Design and Study Demographics .......................................................................................... 23
14.2 Study Results ......................................................................................................................... 24
14.3 Comparative Bioavailability Studies ....................................................................................... 25
15 MICROBIOLOGY ........................................................................................................................... 25
16 NON-CLINICAL TOXICOLOGY ..................................................................................................... 25
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................................. 31
PATIENT MEDICATION INFORMATION ................................................................................................ 33
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
Minoxidil 5% Men / Hommes (5% minoxidil topical foam) is indicated for:
- the treatment of male androgenetic alopecia (male pattern hair loss) on the top of the scalp (vertex).
The effectiveness of Minoxidil 5% Men / Hommes in the treatment of receding hairlines has not been demonstrated in clinical trials.
Minoxidil 5% Men / Hommes: the persistence of effect after cessation of treatment for 16 weeks in men has not been demonstrated in clinical trials.
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics (>65 years of age): The safety and efficacy of Minoxidil 5% Men / Hommes in men over 65 have not been tested in clinical studies.
2 CONTRAINDICATIONS
Minoxidil 5% Men / Hommes is contraindicated:
- in Women
- in individuals with a history of hypersensitivity to minoxidil or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
- in individuals with treated or untreated hypertension.
- in individuals whose baldness is not due to hereditary factors. Minoxidil 5% Men / Hommes is only effective for the treatment of male vertex alopecia androgenetica.
- in individuals with any scalp abnormality (including psoriasis and sunburn).
- in individuals with a shaved scalp or whose scalp’s skin is broken, inflamed, irritated, infected, or severely sunburned.
- if occlusive dressings or other topical therapeutic medications for treating disorders of the skin of the scalp are being used.
Certain prescription and non-prescription medications, certain treatments, such as cancer chemotherapy, or certain diseases, such as iron deficiency, thyroid disorders or secondary syphilis, as well as severe nutritional problems and certain grooming habits (e.g., cornrowing, tight ponytails), may also cause temporary hair loss which should not be treated with Minoxidil 5% Men / Hommes.
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- FOR EXTERNAL USE ONLY. Do not ingest. Use Minoxidil 5% Men / Hommes (5 % minoxidil topical foam) only as directed. Apply Minoxidil 5% Men / Hommes when the hair and scalp are thoroughly dry. The safety and efficacy of Minoxidil 5% Men / Hommes in users aged under 18 or in men over 65 years of age have not been established.
4.2 Recommended Dose and Dosage Adjustment
Minoxidil 5% Men / Hommes
A dose of half (½) capful (equal to 1 gram of foam or 50 mg minoxidil), Minoxidil 5% Men / Hommes should be applied to the total affected hair loss areas of the scalp (not on the hair) twice daily. The total daily dosage should not exceed 2 grams of foam (100 mg minoxidil) in men.
It may take twice-daily applications for 2 months or more before evidence of hair growth can be expected. If hair regrowth occurs, twice daily applications of Minoxidil 5% Men / Hommes are necessary for continued hair growth. Regrown hair may disappear three to four months after stopping Minoxidil 5% Men / Hommes application and the balding process will continue. Treatment should be discontinued if there is no improvement after one year.
Health Canada has not authorized an indication for pediatric use.
4.4 Administration
Minoxidil 5% Men / Hommes
- 1) To open container: Match arrow on can ring with arrow on cap. Pull off cap.
- 2) Hold the can upside down and press nozzle to dispense the foam. The total amount of foam applied should not exceed half (½) capful (equivalent to one gram of foam)
- 3) The foam may begin to melt on contact with warm skin. If your fingers are warm, rinse them in cold water first. Be sure to dry them thoroughly before handling the foam.
- 4) The foam should be massaged lightly into the affected areas of the scalp.
4.5 Missed Dose
Minoxidil 5% Men / Hommes
If one or two applications are missed, the missed application(s) should be skipped, and treatment should be resumed with the next scheduled application/dose. Do not use twice as much, or twice as often, the prescribed dose.
5 OVERDOSAGE
Accidental ingestion of Minoxidil 5% Men / Hommes can cause serious cardiac adverse effects..
Because of the high concentration of minoxidil in Minoxidil 5% Men / Hommes, accidental oral ingestion of this product could result in systemic absorption sufficient to cause the predictable cardiovascular effects of minoxidil (e.g., reduced blood pressure, reflex tachycardia, fluid retention).
Signs and symptoms of overdosage would most likely include cardiovascular effects associated with fluid retention, sudden weight gain, lowered blood pressure and tachycardia, faintness and dizziness. Fluid retention can be managed with appropriate diuretic therapy. Tachycardia can be controlled by administration of beta-adrenergic blocking agent.
Minoxidil and its metabolites are hemodialyzable, although this does not rapidly reverse its pharmacological effect.
Significant toxicity after minoxidil exposure, whether tablet or topical formulations, was associated with oral route, intentional reason, and co-ingestion of other products. A male who ingested 60 mL (one bottle) of 2% minoxidil with 12 ounces of cognac experienced tachycardia, hypotension, and a non-Q wave myocardial infarction. In another report, a patient who inadvertently drank minoxidil solution (he ingested 600 mg), developed syncope, hypotension, and acute renal failure.
. Overdosage occurs very rarely, and the risk profile of the product remains unchanged. The risk mitigation is being taken in labelling.
If exaggerated hypotension is encountered, it is most likely to occur in association with residual sympathetic nervous system blockade from previous therapy (guanethidine-like effects or alpha- adrenergic blockade). The recommended treatment is intravenous administration of normal saline.
Sympathomimetic drugs, such as norepinephrine or epinephrine, should be avoided because of their excessive cardiac-stimulating action. Phenylephrine, angiotensin II, vasopressin and dopamine, which reverse the effects of orally administered minoxidil, should only be used if inadequate perfusion of a vital organ is evident.
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORM, STRENGTH, COMPOSITION AND PACKAGING
Table – Dosage Form, Strength, Composition and Packaging
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Topical | Foam / 50 mg/g (5%) minoxidil | Anhydrous Citric Acid, Butylated Hydroxyl Toluene, Cetyl Alcohol, Dehydrated Alcohol, Glycerin, Hydrocarbon Propellant (propane, isobutane, n-butane), L-Lactic Acid, Purified Water, Polysorbate 60, and Stearyl Alcohol. |
Minoxidil 5% Men / Hommes (5% minoxidil topical foam) is available in a lined (polyamide-imide) aluminum pressurized container with a translucent round dust cap, containing 60 grams of product. Packs contain either one or three cans. The foam is creamy in appearance.
7 WARNINGS AND PRECAUTIONS
General
- Minoxidil 5% Men / Hommes is for external use only. Apply only to scalp. Do not ingest.
- Before applying Minoxidil 5% Men / Hommes, the user should determine that the scalp is normal and healthy.
- Hands should be washed thoroughly after use.
- Inhalation of the spray should be avoided.
- Minoxidil 5% Men / Hommes contain ethanol (alcohol) which will cause burning and irritation of the eye. In the event of accidental contact with sensitive surfaces (eye, abraded skin, mucous membranes), the area should be bathed with large amounts of cool tap water.
- Minoxidil 5% Men / Hommes also contain butylated hydroxytoluene, cetyl alcohol, and stearyl alcohol. Butylated hydroxytoluene may cause local skin reactions (e.g., contact dermatitis), or irritation to the eyes or mucous membranes. Cetyl alcohol and stearyl alcohol may cause local skin reactions (e.g., contact dermatitis).
- Some patients have experienced changes in hair colour and/or texture with Minoxidil 5% Men / Hommes use.
- Shedding of hair may occur within two to six weeks after initiating therapy, likely due to minoxidil’s action on shifting hairs from the resting telogen phase to the growing anagen phase. If shedding persists for more than two weeks, users should stop applying Minoxidil 5% Men / Hommes and consult their doctor.
- Minoxidil 5% Men / Hommes should not be used when there is no family history of hair loss, hair loss is sudden and/or patchy, or the reason for hair loss is unknown.
- Cases of hypertrichosis have been reported in infants following skin contact with minoxidil application site of patients (caregivers) using topical minoxidil. Hypertrichosis was reversible, within months, when infants were no longer exposed to minoxidil. Contact between children and minoxidil application sites should be avoided.
Cardiovascular
- Accidental ingestion may cause serious cardiac adverse events.
- Patients with known cardiovascular disease or cardiac arrhythmia should contact a physician before using Minoxidil 5% Men / Hommes.
- Although the following systemic effects have not been associated with the topical use of Minoxidil 5% Men / Hommes, there is some absorption of minoxidil from the skin and the potential exists for systemic effects such as salt and water retention, hypertension, tachycardia, angina, and edema.
- The patient should stop using Minoxidil 5% Men / Hommes and see a doctor if hypotension is detected or if the patient is experiencing chest pain, rapid heartbeat, faintness or dizziness, sudden unexplained weight gain, swollen hands or feet, or persistent redness.
Monitoring and Laboratory Tests
Patients should be monitored for signs of systemic effects of minoxidil such as hypotension, chest pain, rapid heartbeat, faintness or dizziness, sudden unexplained weight gain, swollen hands or feet, persistent redness or irritation of the scalp. The use of Minoxidil 5% Men / Hommes should be discontinued in the event of systemic effects and/or severe dermatologic reactions.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies in pregnant women using Minoxidil 5% Men / Hommes. This product should not be used in pregnant women.
7.1.2 Breast-feeding
There are no adequate and well controlled studies in breastfeeding women. Systemically absorbed minoxidil is secreted in human milk. Minoxidil 5% Men / Hommes should not be used in nursing women.
7.1.3 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Minoxidil 5% Men / Hommes in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 1.1 Pediatrics.
Accidental ingestion may cause serious cardiac adverse events. Therefore, this product has to be kept out of the reach of children. See 7 Warnings and Precautions, Cardiovascular..
7.1.4 Geriatrics
Geriatrics (> 65 years of age): The efficacy and safety of Minoxidil 5% Men / Hommes in men over 65 years of age have not been established. Minoxidil 5% Men / Hommes should not be used in the male geriatric population.
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Men’s MINOXIDIL FOAM 5%
In the short-term treatment with Men’s Minoxidil FOAM 5% BID in males with androgenetic alopecia (16-week Placebo-controlled phase of Study 006), serious events (1.1% for Minoxidil Foam 5% group and 1.7% for Placebo Foam group) were not considered drug related, and no serious event resulted in discontinuing study participation. Most of the drug-related adverse events (6.7% in the Minoxidil Foam 5% group, 7% in the Placebo Foam group) reflected mild to moderate pain or skin irritation. Adverse events related to study withdrawal (1.7% in the Minoxidil Foam 5% group, 1.2% in the Placebo Foam group) were headache, alopecia, and rash (one case each) in the Minoxidil Foam 5% group, and tachycardia, nausea, and hyperventilation (one case each) in the Placebo Foam group.
The most frequently reported adverse drug reaction following the short-term 16-week treatment with Men’s Minoxidil FOAM 5% was Headache (1.7% for Minoxidil Foam 5%, 1.2% for Placebo Foam).
Dermatological adverse reactions included Pruritis (1.1% for Minoxidil Foam 5%, 0.0% for Placebo Foam), and Rash (1.1% for Minoxidil Foam, 0.0% for Placebo Foam). The most frequently reported dermatological adverse events were erythema (4.0% for Minoxidil Foam 5% group, 4.9% for Placebo Foam group), rash (3.9% for Minoxidil Foam 5%, <1.0% for Placebo Foam), acne (2.8% for Minoxidil Foam 5%, 1.7% for Placebo Foam), and pruritis (2.2% for Minoxidil Foam 5%, 1.2% for Placebo Foam).
The most frequently reported adverse events at week 16 were infections (11.1% for Minoxidil Foam 5%, 12.8% for Placebo Foam), accidental injury (2.8% for Minoxidil Foam 5%, 7.6% for Placebo Foam), pain (2.2% for Minoxidil Foam 5%, 1.2% for Placebo Foam), flu syndrome (2.2% for Minoxidil Foam 5%, 1.7% for Placebo Foam), bronchitis (2.2% for Minoxidil Foam 5%, 1.2% for Placebo Foam), and pharyngitis (2.2% for Minoxidil Foam 5%, 0.0% for Placebo Foam).
Adverse events that differed in incidence of more than 1% in the Minoxidil Foam 5% group relative to the Placebo Foam group at week 16 included headache (7.2% for Minoxidil Foam 5%, 3.5% for Placebo Foam), pharyngitis (2.2% for Minoxidil Foam 5%, 0.0% for Placebo Foam vehicle), hypersensitivity (1.7% for Minoxidil Foam 5%, 0.0% for Placebo Foam), pyrexia (1.1% for Minoxidil Foam 5%, 0.0% for Placebo Foam), and myalgia (1.1% for Minoxidil Foam 5%, 0.0% for Placebo Foam).
For the long-term treatment with Men’s Minoxidil FOAM 5% BID (an open-label safety extension phase of Study 006), 114 subjects out of 143 subjects completed one year of treatment. 53.1% of the subjects reported adverse events. The most frequently reported non-serious adverse events were infection (6.7%), headache (3.7%), and accidental injury (2.3%). Two events were considered serious in nature; accidental injury (<1.0%) and pain (<1.0 %) but were not considered to be drug related. All other adverse events were considered mild or moderate in nature. The incidence of drug-related adverse events was 7.0% of subjects overall and 13.2% of the subjects reporting adverse events. The incidence of adverse events leading to withdrawal was low (2.8% overall).
In general, the overall post-marketing safety experience to date has been consistent with that observed in the clinical trial program.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Men’s MINOXIDIL FOAM 5%
In a randomized, double-blind, placebo-controlled, multi-centre (involving 14 centers) trial (Study 006), the efficacy and safety of a topical 5% Minoxidil Foam formulation for the treatment of male androgenetic alopecia were evaluated. A total of 352 male subjects with androgenetic alopecia were enrolled. Subjects were randomized in a ratio of 1:1 to receive either 5% Minoxidil Foam twice daily (180 subjects) or placebo foam twice daily (172 subjects) for 16 weeks. Safety was assessed by means of clinical assessments of local tolerance, laboratory tests, and vital signs, as well as reported adverse events.
Table 1 summarizes the Adverse Events reported in study 006 for ≥1% of subject by Primary System Organ Class and Preferred Term.
Table 1 Adverse Events occurring in ≥1% of male patients treated with Men’s MINOXIDIL FOAM 5% as compared to male patients treated with Placebo for 16 weeks
| Primary System Organ Class: Preferred Term | Number (%) of Subjects | ||||||
| Primary System Organ Class: Preferred Term | Number (%) of Subjects | ||||||
| Primary System Organ Class: Preferred Term | Number (%) of Subjects | ||||||
5% Minoxidil Foam (N=180) | Foam Vehicle (N = 172) | ||||||
5% Minoxidil Foam (N=180) | Foam Vehicle (N = 172) | ||||||
5% Minoxidil Foam (N=180) | Foam Vehicle (N = 172) | ||||||
| Gastrointestinal Disorders | |||||||
| Abdominal Pain | 2 (1.1) | 1 (<1.0) | |||||
| Diarrhea | 2 (1.1) | 3 (1.7) | |||||
| Gastrointestinal Disorder | 1 (<1.0) | 3 (1.7) | |||||
| Hernia | 2 (1.1) | 2 (1.2) | |||||
| Nausea | 2 (1.1) | 2 (1.2) | |||||
| General Disorders and Administration Site Conditions | |||||||
| Flu Syndrome | 4 (2.2) | 3 (1.7) | |||||
| Pain | 4 (2.2) | 2 (1.2) | |||||
| Pyrexia | 2 (1.1) | 0 (0.0) | |||||
| Periodontal Abscess Complication | 1 (<1.0) | 2 (1.2) | |||||
| Immune System Disorders | |||||||
| Hypersensitivity | 3 (1.7) | 0 (0.0) | |||||
| Infection and Infestations | |||||||
| Infection | 20 (11.1) | 22 (12.8) | |||||
| Infection Viral | 2 (1.1) | 1 (<1.0) | |||||
| Infection Bacterial | 1 (<1.0) | 2 (1.2) | |||||
| Periodontal Abscess Complication | 1 (<1.0) | 2 (1.2) | |||||
| Injury, Poisoning, and Procedural complications | |||||||
| Accidental Injury | 5 (2.8) | 13 (7.6) | |||||
| Metabolism and Nutritional Disorders | |||||||
| Hyperglycemia | 1 (<1.0) | 5 (2.9) | |||||
| Hyperuricemia | 0 (0.0) | 2 (1.2) | |||||
| Musculoskeletal and Connective Tissue Disorders | |||||||
| Arthralgia | 2 (1.1) | 1(<1.0) | |||||
| Myalgia | 2 (1.1) | 0 (0.0) | |||||
| Nervous System Disorders | |||||||
| Headache | 13 (7.2) | 6 (3.5) | |||||
| Dizziness | 1 (<1.0) | 3 (1.7) | |||||
| Psychiatric Disorders | |||||||
| Depression | 1 (<1.0) | 2 (1.2) | |||||
| Renal and Urinary Disorders | |||||||
| Urine abnormality | 4 (2.2) | 6 (3.5) | |||||
| Haematuria | 3 (1.7) | 7 (4.1) | |||||
| Albuminuria | 0 (0.0) | 2 (1.2) | |||||
| Glycosuria | 0 (0.0) | 4 (2.3) | |||||
| Respiratory, Thoracic, and Mediastinal Disorders | |||||||
| Bronchitis | 4 (2.2) | 2 (1.2) | |||||
| Pharyngitis | 4 (2.2) | 0 (0.0) | |||||
| Pneumonia | 1 (<1.0) | 3 (1.7) | |||||
| Rhinitis | 1 (<1.0) | 4 (2.3) | |||||
| Skin and Subcutaneous Tissue Disorders | |||||||
| Rash | 7 (3.9) | 1 (<1.0) | |||||
| Acne | 5 (2.8) | 3 (1.7) | |||||
| Pruritis | 4 (2.2) | 2 (1.2) | |||||
| Photosensitivity Reaction | 1 (<1.0) | 4 (2.3) | |||||
| Dry Skin | 0 (0.0) | 2 (1.2) | |||||
| Vascular Disorders | |||||||
| Hypertension | 2 (1.1) | 1 (<1.0) | |||||
8.3 Less Common Clinical Trial Adverse Reactions
Adverse Drug Reactions observed in <1% of males treated with Men’s MINOXIDIL FOAM 5% for 16 weeks
General Disorders and Administration Site Conditions: headache and pain (not otherwise specified).
Vascular Disorders: hypertension.
Skin and Subcutaneous Tissue Disorders: acne, rash, pruritis, and hirsutism.
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
The following table summarizes the Clinical Chemistry Abnormal Values noted in male patients treated with Men’s Minoxidil 5% FOAM compared to male patients treated with Placebo Foam Vehicle for 16 weeks (STUDY 006).
Table 2: Values at Week 16 vs. Baseline (Men's MINOXIDIL Foam 5% Study 006)
| Notable Criteria | 5% Minoxidil Foam BID | Placebo Foam Vehicle BID | |
| (N=180) | (N =172) | ||
| Parameter | ULN (U/L) | Number (%) of Subjects with | Number (%) of Subjects with |
| Increase > ULN | Increase > ULN | ||
| ALT | 43 | 2 (1.1%) | 0 (0.0) |
| AST | 36 | 3 (1.7) | 2 (1.2) |
| GGT | 61 | 3 (1.7) | 2 (1.2) |
ULN=Upper Limit of Normal, ALT=Alanine aminotransferase, AST=Aspartate aminotransferase, GTT=Gamma-glutamyltransferase.
8.5 Post-Market Adverse Reactions
The following adverse drug reactions (ADRs) have been identified with the application of topical minoxidil during post-marketing use. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to the use of the drug. In Table 6 below, the ADRs are presented with ADR frequency categories estimated from spontaneous reporting rates according to the following convention where the numerator represents the total number of reported Company Adverse Events (AEs) under a given preferred term (PT) or medical concept and the denominator represents exposure data calculated from sales data.
Very common ≥1/10
Common ≥1/100 and < 1/10
Uncommon ≥1/1,000 and <1/100
Rare ≥1/10,000 and <1/1,000
Very rare <1/10,000
Not known (cannot be estimated from the available data)
Table 3: Adverse Drug Reactions Identified During Post-Marketing Experience with Topical Minoxidil by Frequency Category Estimated from Spontaneous Reporting Rates*
| System Organ Class | Adverse Event Preferred Term |
| System Organ Class | Adverse Event Preferred Term |
Immune System Disorders Very rare Very rare Very rare | Angioedema (the manifestations of angioedema may include the following: Lip oedema, Oedema mouth, Oropharyngeal swelling, Pharyngeal oedema, and Tongue oedema) Hypersensitivity (the manifestations of hypersensitivity reactions may include the following: Face oedema, Generalised erythema, Pruritus generalised, and Throat tightness) Dermatitis contact |
Psychiatric Disorders Very rare | Depressed mood |
Nervous System Disorders Very rare | Dizziness |
Eye Disorders Very rare | Eye irritation |
| Cardiac Disorders | |
Very rare Very rare | Tachycardia Palpitations |
Vascular Disorders Very rare | Hypotension |
Gastrointestinal Disorders Very rare Very rare | Nausea Vomiting |
Skin and Subcutaneous Tissue Disorders Very rare Very rare Very rare Very rare | Application site reaction (these sometimes involve nearby structures like the ears and face and typically consist of pruritus, irritation, pain, rash, oedema, dry skin, and erythema but can sometimes be more severe and include exfoliation, dermatitis, blistering, bleeding, and ulceration) Alopecia Hair colour changes Hair texture abnormal |
General Disorders and Administration Site Conditions Very rare | Chest pain |
*Patient exposure was estimated by calculation from sales data from IMS MIDASTM
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
There are currently no known drug interactions associated with concomitant use of systemic drugs and topical minoxidil. Absorption of topical minoxidil is controlled and rate-limited by the stratum corneum. However, there is a potential risk that the minoxidil in Men’s Minoxidil FOAM 5% may interact with vasodilators, e.g., hydralazine.
9.3 Drug-Behavioural Interactions
Interactions with lifestyle have not been established.
9.4 Drug-Drug Interactions
Topical drugs, e.g., tretinoin and anthralin, which alter the stratum corneum barrier, could result in increased absorption of topical minoxidil if applied concurrently. Betamethasone dipropionate has been shown to increase local tissue concentrations of Minoxidil and decreases systemic Minoxidil absorption in healthy volunteers. However, the effect of Betamethasone dipropionate on Minoxidil absorption with an inflamed scalp is not known. Although it has not been demonstrated clinically, there exists the theoretical possibility of absorbed Minoxidil potentiating orthostatic hypotension caused by peripheral vasodilators.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
When applied topically, minoxidil has been shown to stimulate hair growth in males with androgene tic alopecia. The basic change in androgenetic alopecia is the conversion of terminal, non-vellus hair to vellus hair, i.e., hair which is thinner, shorter, and less pigmented.
Although the exact mechanism of action of minoxidil in the treatment of androgenetic alopecia is not known, there may be more than one mechanism by which minoxidil stimulates hair growth; they include:
- vasodilation of the micro circulation around the hair follicles which may stimulate hair growth
- direct stimulation of the hair follicle cells to enter into a proliferative phase; resting phase (telogen)
- follicles being stimulated to pass into growth phase (anagen) follicles.
10.2 Pharmacodynamics
The hemodynamic effects of minoxidil do not correlate directly with serum levels. There is a delay in onset relative to observable serum concentrations, peak hemodynamic effects lag one hour behind peak serum concentrations, and hemodynamic effects persist long after nearly all the minoxidil has disappeared from the circulation. It appears that minoxidil requires bioactivation before exerting its hemodynamic activity. The active metabolite is considered to be minoxidil sulphate. Sulfotransferase enzyme which converts minoxidil to minoxidil sulphate has been isolated from various human tissues including liver, platelets, scalp skin, hair follicles and epidermal keratinocytes. The effects of minoxidil on hair regrowth are possibly mediated by this active metabolite as well. In clinical studies, no correlation was established between serum or tissue minoxidil concentrations and hair regrowth.
In Vitro/in Vivo Studies
Exploratory in vivo and in vitro studies, designed to determine the mechanism by which minoxidil stimulates hair growth in patients with male pattern baldness have been completed, but have not been successful in definitely demonstrating the mechanism of action of minoxidil in stimulating hair growth. Studies have shown that there appears to be an immediate vasodilation of the micro circulation after topical application of minoxidil and that there is no significant alteration of the effects of androgens on scalp hair. These studies have also shown that cultured epidermal cells appear to be stimulated to divide under the influence of minoxidil and that in vitro cell cultures of lymphocytes are inhibited in their response to mitogens when minoxidil is present in culture. The overall significance of any of these studies is unknown.
In Vivo Studies
Results of two studies evaluating minoxidil tablets in doses up to 5 mg twice daily for up to 28 days in normotensive patients show that there were no clinically significant effects on blood pressure measurements or on pulse rate. In addition, there were no clinically significant changes in maximum heart rate response to standard treadmill test, pulse and blood pressure response to a dynamometer grip device, forearm blood flow, plasma renin levels or urine epinephrine and norepinephrine levels.
No evidence of fluid retention was seen. The conclusion was made that low-to-moderate, short-term doses of minoxidil tablets, in normotensive volunteers, do not lower blood pressure, and side effects commonly observed during minoxidil tablet therapy for hypertensive patients do not occur in normotensive subjects.
No clinically significant systemic effects were noted in a 16-week, placebo-controlled, randomized study of 98 treated hypertensive patients (involving B-blockers, diuretics) who were also treated with minoxidil topical solution 3%.
Untreated hypertensive patients were evaluated in an IV minoxidil study. The subjects achieved pharmacokinetic steady state within 6 hours after the start of infusion. The heart rate and diastolic blood pressure effects observed indicated that IV infusions of 1.37 mg and 3.43 mg of minoxidil did not result in clinically significant cardiovascular effects. The 6.86 mg dose, which resulted in a mean serum minoxidil concentration of 21.7 ng/mL, was the lowest dose clearly distinguishable from placebo, based on heart rate data.
Immune Function
A pilot study compared the immune status of 11 patients with male pattern baldness who were treated with topical minoxidil for 30 months, with the immune status of 12 untreated male control subjects.
Peripheral leukocytes were examined for the presence of various cell subpopulations using monoclonal antibodies coupled with cytofluorometry and for blastogenic responses to phytohemagglutinin (PHA), concanavalin A (Con A), and pokeweed mitogen (PWM). The results of this study revealed no effect on helper T-cell, suppressor T-cell, B-cell, or natural killer cell numbers. In addition, no difference was observed in mitogenic responses of the minoxidil-treated patients (to any of the mitogens) as compared to responses of the control subjects.
Effect on Cardiac Function
An analysis of echocardiographic parameters such as left ventricular diameters in systole and diastole, septal and posterior wall thickness, cardiac output and cardiac index revealed no differences in patients exposed to 3% minoxidil solution for up to 5 years when compared to healthy patients that had not been exposed to 3% minoxidil during this time period.
10.3 Pharmacokinetics
Absorption
Absorption of topical minoxidil averages about 1.4% (range 0.3 to 4.5%) from normal intact scalp. Absorption is about 2% when applied topically to shaved scalps of hypertensive patients. Increasing the amount of drug applied or increasing the frequency of application of topical minoxidil also results in increased absorption. The use of minoxidil in conjunction with occlusion (plastic dressing) application to sunburn areas and increasing the surface area of application has minimal to no effect on the absorption of topical minoxidil.
Results of extensive pharmacokinetic studies indicate that the three major factors by which topical minoxidil absorption is increased are:
- increasing the magnitude of the dose applied
- increasing the frequency of dosing; and
- decreasing the barrier function of the stratum corneum.
The following table provides serum minoxidil concentrations measured in clinical efficacy studies.
Table 4: Serum concentrations of total minoxidil after the application of 1 mL of Men’s Minoxidil twice daily
Serum minoxidil concentratio n (ng/mL) | Interval of exposure to Treatment | Summary | ||||||||||||||||||||
0-6 mths N | 7-12 mths N | 13-24 mths N | 25-36 mths N | 37-54 mths N | N | % | Cumulative % | |||||||||||||||
| <0.1 | 601 | 320 | 211 | 121 | 84 | 1337 | 31.2 | 31.2 | ||||||||||||||
| 0.1-2.0 | 1082 | 692 | 510 | 340 | 140 | 2764 | 64.5 | 95.6 | ||||||||||||||
| 2.1-5.0 | 65 | 38 | 28 | 17 | 7 | 155 | 3.6 | 99.3 | ||||||||||||||
| 5.1-8.0 | 6 | 3 | 2 | 4 | 0 | 15 | 0.3 | 99.6 | ||||||||||||||
| 8.1-12.0 | 4 | 3 | 2 | 0 | 0 | 9 | 0.2 | 99.8 | ||||||||||||||
| 12.1-15.0 | 1 | 0 | 0 | 0 | 0 | 1 | 0 | 99.8 | ||||||||||||||
| 15.1-18.0 | 1 | 0 | 0 | 0 | 0 | 1 | 0 | 99.9 | ||||||||||||||
| 18.1-21.0 | 0 | 1 | 0 | 0 | 1 | 2 | 0 | 99.9 | ||||||||||||||
| > 21.0 | 1 | 3 | 0 | 0 | 0 | 4 | 0.1 | 100 | ||||||||||||||
| Total | 1761 | 1060 | 753 | 482 | 232 | 4288 | 100 | 100 | ||||||||||||||
Although the percutaneous drug absorption data are highly variable, the table shows that more than 99% of the values are below 5 ng/mL and less than 0.2% exceeds 12 ng/mL.
Absorption from the gastrointestinal tract following oral administration of minoxidil tablets is essentially complete (at least 95%).
In Vivo studies
Extent of Absorption
A three-way cross-over study in 14 male volunteers demonstrated that the extent of minoxidil absorption, by the topical route, is low; with bioavailability averaging 1.4% and 1.2%, for 2% and 3% topical solutions respectively, relative to oral doses of 2.5 mg minoxidil tablet.
The disappearance of minoxidil from the systemic circulation was found to be controlled by its rate of absorption, which is slow, and appears to occur by a zero-order process at steady state. Absorption of minoxidil from topically applied solution is greater in individuals with whom a simulated bald spot was generated by shaving (2.4% of applied dose) than in individuals who were naturally bald (1.4% of applied dose).
A four-way cross-over study in 23 male subjects demonstrated that the contact time of Men’s Minoxidil Topical Solution affects absorption. Treatment involved dosing of 1mL q12h for 6 days applied to a constant surface area of the scalp. The scalp was washed one, two, four, and 11.5 hours post dose. With increased contact time, absorption increased disproportionately. More than 50% of the minoxidil that is eventually absorbed is absorbed in the first hour post dose, and absorption is nearly complete after 4 hours.
The concomitant topical application of minoxidil with corticosteroids or tretinoin cream causes an increased absorption of minoxidil.
Effect of Surface Area
A four-way cross-over study documented that when 1 mL of 2% minoxidil solution was spread over surface areas ranging from 100 cm2 to 200 cm2, the amount of minoxidil absorbed was minimally affected. Less than a 20% increase in the amount absorbed was observed with a 100% increase in surface area.
Dose Proportionality
Results of a parallel design study of subjects applying 1 mL of a 0.01%, 0.1%, 1%, or 2% minoxidil solution twice daily to the scalp for two weeks indicate that absorption increases nearly linearly over the dose range studied. A cross-over study evaluating higher strength solutions demonstrated that the amount of minoxidil recovered in the urine increases less than in proportion to an increase in dose for the dose range evaluated. Subjects in this study had applied 1 mL of a 1%, 2%, or 5% solution to a constant 200 cm2 surface area every 12 hours.
Frequency of Application
Percutaneous absorption is increased when the frequency exceeds twice daily dosing. Absorption for minoxidil that is applied to a healthy scalp does reach a threshold maximal level. It has been documented that the average amount of minoxidil recovered in the urine following 1 mL of 1% minoxidil solution administered every six hours was equivalent to that observed following 1 mL of 2% minoxidil administered every 12 hours.
Volume of Solution
A cross-over study evaluated the effect of the volume of application on the amount of minoxidil absorbed. This study documented that for a constant applied dose (10 mg) over a constant surface area, the volume applied has no influence on the amount of drug absorbed. Subjects received 1 mL of 1% minoxidil solution, 2 mL of 2% minoxidil solution, and 1/3 mL of 3% minoxidil solution.
Location of Application
No significant accumulation of minoxidil occurred as a result of applying up to four times the recommended dose of 3% minoxidil solution to the scalp or chest. In this parallel-design study, subjects received 1 mL of 3% minoxidil solution (30 mg) between two and eight times within a 12-hour interval for fourteen consecutive days. The results also demonstrated that there was no difference in absorption of minoxidil between the scalp and chest if applied less than eight times per day. Absorption of minoxidil appeared to be slightly greater in the scalp than in the chest at eight applications per day.
Overall, the results indicate that absorption of minoxidil solution was independent of the number of applications within a twelve-hour period for the doses administered in this study. This dosage range (60 to 240 mg per day) was significantly greater than that used in previous studies which demonstrated a significant but less than proportional increase in the amount absorbed, following doses of 10 to 50 mg. The lack of an increase in serum or urine minoxidil levels with increased frequency of application seen in this study is probably the result of saturation of the stratum corneum with initial doses of minoxidil.
After application of minoxidil topical solution 2% q12h to the scalp, forearm, and upper back, it has been shown that systemic absorption is three-fold greater after application to the scalp compared to the forearm or back.
Animal Data
In Vivo studies
Results from a long-term dermal toxicity study in rats concluded that there was no apparent relationship between the nadir minoxidil levels and gross cardiac pathology. These nadir minoxidil levels in the rat were approximately 40 to 500 times higher than those documented in humans.
Results from a long-term dermal toxicity in rabbits concluded that increased heart and liver weights were drug-related; however, no concomitant histopathologic lesions were seen.
The following table provides a comparison of topically absorbed doses from a 2-year dermal carcinogenicity study in mouse and rat, compared to results obtained from humans using the recommended twice daily dose of Men’s Minoxidil Topical Solution. The table demonstrates that on a mg/kg basis, the animals received higher doses than humans. In addition, the % minoxidil absorbed was much higher in the animals.
Both of these factors indicate that the systemic exposure to minoxidil in animals (in preclinical toxicity studies) is several hundred times greater than that associated with clinically recommended doses in man.
Table 5: Comparison of Minoxidil Absorption from different doses in Mouse and Rat to that from Men’s Minoxidil Topical Solution BID in Humans
| Mouse | Rat | Man | ||||||||||||||||
Dose (mg/kg/day) | 8 | 25 | 80 | 8 | 25 | 80 | 0.57 | |||||||||||
| % absorbed | - | 47.6 | - | - | 32.4 | - | 1.4 | |||||||||||
Available dose (mg/kg/day) | 3.8 | 11.9 | 38.1 | 2.59 | 8.10 | 25.9 | 0.009 | |||||||||||
Ratio (animal/man) | 422 | 1322 | 4233 | 288 | 900 | 2878 | 1.0 | |||||||||||
Following topical application, the urinary metabolite profiles in the rat corresponded closely to those observed after systemic administration, suggesting that metabolism was not altered by entry across the skin.
Characteristics of the topical absorption of 14C-labelled minoxidil differ appreciably in monkey scalp. During the 10-16 days the monkeys were chaired, approximately 4% of the 1% solution and 1% of the 4% solution appeared in the urine. When returned to metabolism cages, a larger component of total urinary excretion occurred; urinary excretion did not follow first order kinetics. Total absorption in the monkeys was 17.4% of a 1% solution and 5.7% of a 4% solution.
Distribution:
Minoxidil does not bind to plasma proteins; its renal clearance corresponds to glomerular filtration rate, and it does not cross the blood brain barrier. Minoxidil and its metabolites are hemodialyzable, although this does not rapidly reverse its pharmacological effect.
Metabolism:
Approximately 90% of orally administered minoxidil is metabolized, predominantly by conjugation with glucuronic acid at the N-oxide position in the pyrimidine ring and by conversion to more polar products.
In Vitro Studies
The transdermal metabolism of 14C-minoxidil in fresh human skin in an in-vitro diffusion system was studied. The dermal metabolism of minoxidil in human skin under these in-vitro conditions was minimal at 4.8 to 6.0% of the applied dose.
Elimination
Serum minoxidil levels and systemic effects resulting from administration of topical minoxidil are governed by the drug's absorption rate through the skin. Following cessation of topical dosing of minoxidil, approximately 95% of systemically absorbed drug is eliminated within four days. Minoxidil and its metabolites are excreted principally in the urine.
11 STORAGE, STABILITY AND DISPOSAL
Minoxidil 5% Men / Hommes should be stored at controlled room temperature range of 15-30 °C. Do not puncture or incinerate container. Do not expose to heat or temperature above 50°C. Store in upright position.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: minoxidil
Chemical name: 2,4,-Pyrimidinediamine,6-(1-piperidinyl)-,3-oxide
Molecular formula and molecular mass: C9H15N5O; 209.25
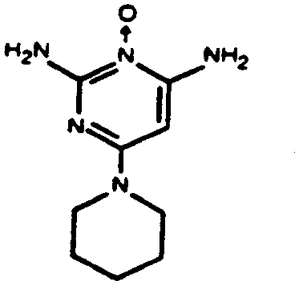
Structural formula:
Physicochemical properties: A white or off-white, crystalline solid that is slightly soluble in water, soluble in propylene glycol and in alcohol, sparingly soluble in methanol, and practically insoluble in acetone, chloroform, ethyl acetate and in hexane. It melts in the approximate range of 248°C.
14 CLINICAL TRIALS
14.1 Trial Design and Study Demographics
Men’s MINOXIDIL FOAM 5% (Minoxidil 50mg/g [5% w/w])
The efficacy of minoxidil 5% foam was evaluated in a Phase 3, randomized, double-blind, placebo-controlled, multi-centre trial involving 14 centers (Study 006). In this study, the efficacy of a topical 5% Minoxidil Foam formulation was compared to that of the product vehicle without the minoxidil active ingredient for the treatment of male androgenetic alopecia. A total of 352 male subjects with androgenetic alopecia were enrolled. Subjects were randomized in a ratio of 1:1 to receive either 5% Minoxidil Foam twice daily (180 subjects) or Placebo Foam twice daily (172 subjects) for 16 weeks. More than 80% of the subjects in each group were Caucasians. The primary efficacy endpoints were the mean change in non-vellus hair count within the target region between Baseline and Week 16, as determined by a validated computer-assisted dot-mapping technique, and subject rating of treatment benefit via the use of global photographs of the vertex region, assessed as an overall improvement from baseline, and collected on a subject questionnaire.
Table 6: Summary of Patient Demographics in Study 006
| Study # | Study design | Dosage, route of administration and duration | Study subjects (n) Minoxidil/ Placebo | Mean age (Range) Minoxidil/ Placebo | Sex |
| 006 | Phase 3, multiple- centre, double-blind, randomized placebo- controlled study, 16 weeks | 5% minoxidil topical foam or placebo, twice daily, topical application to the affected area on the scalp | 172 / 180 | 40.1 (21-49) / 38.3 (20-49) | Male |
| Open label safety phase following the 16-week controlled study, duration up to one year | 5% minoxidil topical foam or placebo, twice daily, topical application to the affected area on the scalp | 75/68 | 39.6 (21-49) | Male |
14.2 Study Results
Men’s MINOXIDIL FOAM 5% (Minoxidil 50mg/g [5% w/w])
The Minoxidil 5% Foam treatment group showed a statistically significant greater increase in hair count compared to the Vehicle Foam group (21.0 versus 4.3 hairs per cm2) at week 16. A clear difference between treatment groups was evident at week 8, increasing at week 12, and again at week 16. The subject’s rating of treatment benefit was statistically significantly better for the Minoxidil 5% Foam treatment group compared to the Placebo treatment group (1.4 vs. 0.5) at week 16.
Table 7: Summary of Efficacy Results for Men’s MINOXIDIL FOAM 5% after 16 weeks of treatment in the controlled-phase of Study 006
| Primary Endpoints | Minoxidil FOAM 5% Mean Scores | Placebo Foam Vehicle Mean Scores |
| Primary Endpoints | Minoxidil FOAM 5% Mean Scores | Placebo Foam Vehicle Mean Scores |
| Mean change in non-vellus hair count in the target region between baseline and weeks 8,12 & 16 | Week 8: 16.0 hairs/cm2 Week 12: 19.9 hairs/cm2 Week 16: 21.0 hairs/cm2 P<0.0001 at each visit | Week 8: 4.9 hairs/cm2 Week 12: 4.5 hairs/cm2 Week 16: 4.3 hairs/cm2 |
Subject rating of treatment benefit based on global photographs of change from baseline | Week 16: 1.4 points P<0.0001 | Week 16: 0.5 points |
14.3 Comparative Bioavailability Studies
Minoxidil 5% Men / Hommes (Minoxidil Foam, Aerosol Foam 50 mg/g (5% w/w)) has satisfied the criteria for a biowaiver in comparison to Men’s ROGAINE® FOAM 5% (Minoxidil Foam 50 mg/g (5% w/w)) (Johnson & Johnson Inc).
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology:
Acute Toxicity
Table 8: LD50 (mg/kg) in Mouse and Rat by Route of Administration
| SPECIES | ROUTE | LD50(mg/kg) | |||||
| Mouse | Oral | 2457 | |||||
| Intraperitoneal | 1001 | ||||||
| Intravenous | 51 | ||||||
| Rat | Oral | 1321 | |||||
| Intraperitoneal | 759 | ||||||
| Intravenous | 49 | ||||||
| Rat | Cutaneous | LD50 (mg/kg) | |||||
| ≥2007 | |||||||
Signs of Toxicity
CNS depression and acute pulmonary congestion.
Concomitant therapy with either prednisone and anti-thymocyte globulin, hydrochlorothiazide and propranolol, or digoxin and furosemide did not appreciably alter the LD50 for minoxidil. Acute toxicity evaluations of cutaneous administration of minoxidil did not result in mortalities at 999 and 1998 mg/kg, therefore the LD50 was not determined.
Repeat Dose Toxicity
Oral Studies
3-Day Studies (Rat, Dog)
Minoxidil was administered orally to rats and dogs at daily doses up to 100 and 10 mg/kg/day respectively for 3 days. In rats, a dose related slight increase in the number of mitoses in hepatocytes was seen. In beagle dogs, epicardial and myocardial cellular infiltrations, hypertrophy and hyperplasia of the mesothelial cells, small focal hemorrhages, and myocardial atrial lesions were observed at 1.0 and 10 mg/kg doses. These findings were more frequent and severe at the higher dose. In mongrel dogs, there were minimal to mild subepicardial hemorrhages present in the right atrium and/or right auricle which may represent the early stages of right atrial lesions as seen in the longer-term studies.
1-Month Studies (Monkey, Dog, Minipig, Rat)
Minoxidil was administered orally to monkeys at 20 mg/kg/day; to dogs at 0.5 and 1 mg/kg/day, and at 20 and 100 mg/kg/day; to minipigs at 20 mg/kg/day; and to rats at 300 mg/kg/day. Grossly observed cardiac hypertrophy was reported in the monkey study (the 4-OH metabolite of minoxidil at the same dose showed no effect). In dogs, lesions of the right atrium and/or auricle were seen at all doses. Local myocardial cell atrophy and/or degeneration were reported at doses as low as 1 mg/kg/day. The 20 mg/kg dose produced degenerative right auricular heart lesions as did the 4-OH metabolite of minoxidil. The high dose resulted in the death of all dogs probably due to profound alteration in electrolyte balance. In the minipig study blood pressure was depressed, heart rate elevated, and total body water and exchangeable sodium were increased. Cardiac lesions due to minoxidil were not seen. In rats, repression of body weight gain, decreased food consumption, reduced erythrocyte levels increased liver and heart weights, indications of cardiac hypertrophy and electrolyte imbalance were observed.
1-Year Studies (Rat, Monkey, Dog)
Minoxidil was administered orally to rats at 10, 30 and 100 mg/kg/day, monkeys at 3.5, 7 and
14 mg/kg/day and dogs at 3, 10 and 30 mg/kg/day. In rats, repression in body weight gain occurred and a dose related increase in liver, kidney, adrenal and heart weights was seen. One high dose female monkey with chronic glomerulonephritis died from cardiac failure and minoxidil probably contributed because of its salt and water retaining action. In the dog study, degenerative right auricular heart lesions were found at all dose levels. Evidence of chronic electrolyte disturbance was noted in dogs at the highest dose.
22-Month Study (Rat)
Minoxidil was administered orally to rats at 3, 10 and 30 mg/kg/day. Increased heart weights were observed at the highest dose. No carcinogenic potential was apparent.
Topical Application Studies
91 - Day (Beagle Dog)
Minoxidil was administered topically to male and female dogs at doses of 0.6, 1.2 and 4.8 mg/kg/day. Hemorrhagic atrial lesions were seen in the right atrium of the heart at all doses over a treatment period of 91 days. Cardiomyopathy and epicarditis of the atrial wall, increased organ weights and decreased inorganic phosphorous levels were reported. The hemorrhagic right atrial lesions reported in this study have not been observed in seven other species (including man) following minoxidil administration.
13-Day (Beagle Dog)
14C-minoxidil was administered topically and orally to female dogs at a dose of 4.8 mg/kg/day for 3 days followed by non-radioactive minoxidil for 10 days. Hemorrhagic right atrial lesions, papillary muscle necrosis/paleness and epicarditis of the right atrium were evident in topically and orally treated groups. Since the percutaneous absorption of minoxidil in dogs is 39% and 2 - 4% in man, the potential of the development of right atrial lesions is not applicable to man.
Other Topical Application Studies
Rat
Notable toxicity was seen only in topical studies done in rats. When Men’s Minoxidil Topical Solution was administered topically to rats, approximately 32% of the dose was absorbed. Therefore, 1 mL of Minoxidil 1% topical solution applied twice daily (20 mg/day), represents 2476 times the human topical dose on the basis of a 250 g rat, a 50 kg human, 32% absorption in rats and an average of 1.4% absorption in man. One mL of Minoxidil 5% topical solution applied twice daily (100 mg/day) represents 12381 times the human topical dose.
In the 94-day dermal rat study (1 mL/day), signs of toxicity were mainly noted in the 6% minoxidil solution group (60 mg/day). The toxicity consisted of dose-related increased nasal and ocular porphyrins; area of soreness in the treatment area (also noted in one control rat); and fecal stains in a few rats of the 6% group. Females had decreased body weight gains, and the following organ weight changes were seen: increased spleen weights for both sexes at all dose levels; increased heart weights for males at all dose levels and for females in the 1% group (10 mg/day); and increased liver weights for males in the 3% (30 mg/day) and 6% (60 mg/day) groups. There were, however, no drug-related lesions involving the skin or internal organs.
A one-year dermal toxicity study in male and female rats at doses of 1 mL b.i.d. of 1%, 3% and
5% minoxidil resulted in decreased body weight gains, increased urinary protein, slight enlargement and/or dilatation of the heart, increased organ weights and histopathologic findings such as cardiac and hepatocellular hypertrophy, myocardial degeneration and increased nephritis. Most of the effects were evident in the 3% (60 mg/kg/day) and the 5% (100 mg/kg/day) groups.
The decreased body weights in females, increased organ weights and histopathologic findings are associated with high systemic doses of minoxidil and, therefore, do not constitute new findings. The systemic doses reached in this study are approximately 2,000 to 12,000 times the human topical dose. The minimal irritation and thickening of the skin were not considered drug-related or of consequence.
Rabbit
On a volume basis (4 mL/day), the dose levels tested in rabbits represent one to five times the human dose. However, on the basis of a 2.5-kg rabbit and a 50-kg man, the dose levels represent 20 to 100 times the human topical dose of Men’s Minoxidil Topical Solution. The absorption of topical applications of Men’s Minoxidil Topical Solution has not been investigated in the rabbit.
In the 21-day dermal study in the rabbit, drug-related clinical signs were absent. Relative and/or absolute heart weights were significantly increased in the males which received the 3% and 5% minoxidil topical solutions, as compared to the controls. No histopathologic lesions were seen.
A one-year dermal toxicity study in male and female rabbits at doses of 2 mL b.i.d. of 1%, 3% and 5% minoxidil resulted in dilated ventricles of the heart, increased organ weights, and slight to moderate irritation. Except for site irritation, none of these effects were evident in the 1% group.
Eye Irritation Studies
A single 0.1 mL dose of a 2% minoxidil solution was instilled into the conjunctival sac of the right eye of New Zealand white rabbits. The left eye served as a control. It was concluded that minoxidil topical solution 2% is an irritant.
A single 100 mg dose of 2% minoxidil gel was instilled into the conjunctival sac of the right eye of three male and three female New Zealand White rabbits. The left eye was untreated and served as control. At one-hour post-instillation, all six treated eyes exhibited slight-to-moderate conjunctival irritation, as indicated by slight redness, slight-to-moderate swelling, and discharge. By 24 hours, the eye irritation remained at approximately the same level for five rabbits, while the irritation in the eye of one female rabbit deteriorated to include slight corneal opacity and iridal capillary injection. However, the irritation gradually subsided by 96 hours post-dosing. By day 7 post-treatment, all the treated eyes appeared normal.
A single 100 mg dose of 3% minoxidil gel was instilled into the conjunctival sac of the right eye of three male and three female New Zealand White rabbits. The left eye was untreated and served as control. Slight-to-moderate conjunctival redness and swelling, and slight-to-severe discharge were observed in all treated eyes from 1-96 hours post-dosing.
In addition, the treated eyes of two males and one female also exhibited slight corneal opacity and corneal epithelial exfoliation for 1-24 hours post-dosing. However, the treated eyes of all six rabbits appeared normal by day 7 post-treatment.
Gel formulations of minoxidil used in the eye irritation studies; contain the same excipients that are present in Men’s Minoxidil Topical Solution, with the exception that a gelling agent and a stabilizer are present in the gel formulation. The alcohol content in the gel formulations is lower than that of the topical solution. Since alcohol is a known eye irritant, it can be concluded that Men’s Minoxidil Topical Solution is also an eye irritant.
Phototoxic/Photoallergic Study
Guinea Pig
Minoxidil topical solution 2% in guinea pigs caused no reaction in a phototoxicity/photoallergic study.
Carcinogenicity: Two-year carcinogenicity studies of minoxidil have been conducted by the dermal and oral (dietary) routes of administration in mice and rats.
In the two-year dermal study in mice, an increased incidence of mammary adenomas and adenocarcinomas in the females at all dose levels (8, 25 and 80 mg/kg/day) was attributed to increased prolactin activity. Mechanistic studies in female mice objectively demonstrated an increased prolactin secretion in mice treated topically with minoxidil for 90 days.
Other hormonal changes, including decreased LH, FSH, and estrogen, which are consistent with hyperprolactinemia, were also observed in these studies. In addition, histological changes consistent with a hyperprolactinemic state were observed in the 90 day and 2-year studies. Hyperprolactinemia is a well-known mechanism in the enhancement of mouse mammary tumors but has not been associated with mammary tumorigenesis in women. Additionally, topical minoxidil has not been shown to cause hyperprolactinemia in women on clinical trials. Absorption of minoxidil through rodent skin is greater than would be experienced by patients treated topically with minoxidil for hair loss. In a dietary study of minoxidil in mice for up to 2 years, malignant lymphomas were seen earlier in females which failed to survive for 2 years in the high dose (63 mg/kg/day) compared to controls. However, this finding was not observed in 2-year topical studies and higher systemic studies. In the 2-year dermal study in mice there was an increased incidence of hepatic nodules in males (63 mg/kg/day); however, there was no effect of dietary minoxidil on malignant lymphomas.
In the two-year dermal study in rats there were significant increases in incidence of pheochromocytomas in males and females and preputial gland adenomas in males. Mechanistic studies in male rats objectively demonstrated an increased prolactin secretion in rats treated topically with minoxidil for 90 days.
Other hormonal changes consistent with hyperprolactinemia in males were also observed in these studies. The increased incidence of preputial gland adenomas observed in male rats is consistent with the increased prolactin levels observed in this species and sex.
Changes in incidence of neoplasms found to be increased in the dermal or oral carcinogenicity studies were typical of those expected in rodents treated with other hypotensive agents (adrenal pheochromocytomas in rats), treatment-related hormonal alterations (mammary carcinomas in female mice; preputial gland adenomas in male rats) or representative of normal variations within the range of historical incidence for rodent neoplasms (malignant lymphomas, liver nodules/adenomas in mice). Based on differences in absorption of minoxidil and mechanisms of tumorigenesis in these rodent species, none of these changes were considered to be relevant to the safety of patients treated topically with minoxidil for hair loss.
There was no evidence of epithelial hyperplasia or tumorigenesis at the sites of topical application of minoxidil in either species in the 2-year dermal carcinogenesis studies. No evidence of carcinogenicity was detected in rats or rabbits treated topically with minoxidil for one year. Topical minoxidil (2% and 5%) did not significantly (p< 0.05) reduce the latency period of UV light-initiated skin tumors in hairless mice, as compared to controls, in a 12-month photocarcinogenicity study.
Positive carcinogenicity findings which occurred in the topical rodent studies did not occur in the oral studies. A comparative bioavailability study using the identical routes and methods of administration used in the topical and oral (drug-in-diet) studies indicated that a 45-fold Cmax and a 3-fold Cav higher systemic exposure to minoxidil occurs after topical vs oral treatment in rodents. Additionally, a study which compared the route dependent absorption, excretion and metabolism of minoxidil-[14C] after topical and oral administration in the female mouse and rat suggested intrinsically greater percutaneous absorption of the topically applied minoxidil-[14C] in the mouse relative to that in the rat.
Genotoxicity: Minoxidil was not genotoxic in the Salmonella (Ames) test (TA-98-100, TA-98-1535, TA-98- 1537, TA-98-1538), the DNA damage alkaline elution assay, the in vitro rat hepatocyte unscheduled DNA synthesis (UDS) assay, the rat bone marrow micronucleus assay, or the mouse bone marrow micronucleus assay. An equivocal result was recorded in an in vitro cytogenetic assay using Chinese hamster ovary cells at long exposure times, but a similar assay using human lymphocytes was negative.
Reproductive and Developmental Toxicology: Male rats received minoxidil in oral doses of 3 or 10 mg/kg/day for 60 days prior to and during the 14-day breeding period. Female rats received the same dose for 14 days prior to and during breeding, and throughout gestation. A reduction in conception rate was observed. No increase in the incidence of fetal resorption in treated dams was seen. The average number of live pups per litter was significantly decreased in both treatment groups, but live pups from treated dams were significantly heavier than live pups from control dams.
Minoxidil, when given orally to pregnant rats and rabbits on gestation days 6 through 15 and
18 respectively, at dose levels of 3 and 10 mg/kg/day showed no teratogenic effect. Increased fetal resorption occurred in rabbits. The same dose administered to rats from the 15th day of gestation until pups were weaned at 21 days showed no effect of treatment on various parameters related to gestation, parturition and lactation.
When a minoxidil suspension was given subcutaneously to pregnant rats in doses of 0,1,11, and
120 mg/kg, no teratogenic changes were found in the fetuses from the rats dosed at 0, 1 and 11 mg/kg of minoxidil. Increased fetal mortality, still birth, external malformations and skeletal anomalies and variations were observed at 120 mg/kg. This dose also caused decreased maternal weight gain and food consumption and thus the fetal effects noted could have resulted from maternal toxicity.
Minoxidil administered subcutaneously to pregnant rats at 80 mg/kg/day was maternally toxic (manifested by general malaise and weight loss) but not teratogenic. This is about 2000 times the maximum daily systemic human exposure after topical administration.
Higher doses (120 and 160 mg/kg/day) produced some fetal malformations. The no adverse effect level (NOAEL) for maternal toxicity was 40 mg/kg/day while the NOAEL for developmental toxicity was 80 mg/kg/day.
Special Toxicology:
Cardiovascular Mechanistic Studies (dog): The mechanisms of the various cardiovascular lesions induced by minoxidil are considered to be related to the exaggerated pharmacologic/hemodynamic effects of the drug rather than to a direct toxicity of the drug. The mechanism of cardiovascular toxicity of minoxidil (an ATP-sensitive potassium channel opener) was studied by blocking its pharmacologic effects with glyburide (an ATP-sensitive potassium channel antagonist) in beagle dogs that were treated orally for two days either with minoxidil alone or in combination with glyburide. Glyburide did not influence the pharmacokinetics of minoxidil but prevented or markedly attenuated the minoxidil- induced carotid pulsation, hypotension, and tachycardia. None of the cardiovascular lesions (right atrial hemorrhagic lesions, subendocardial necrosis, or coronary arteritis) occurred in dogs whose minoxidil - induced hemodynamic effects were effectively blocked by glyburide. These findings led to the conclusion that the cardiovascular toxicity of minoxidil in dogs is related to its exaggerated pharmacologic (hemodynamic) effects rather than by a direct toxic effect of minoxidil on the heart.
The threshold serum concentrations of minoxidil for hemodynamic effects and cardiovascular lesions were determined in dogs administered minoxidil by continuous infusion at doses ranging from 0.05 to 4.32 mg/kg/day for three days. Classic minoxidil-induced cardiovascular lesions were observed after profound hemodynamic changes occurred at doses of 0.43 mg/kg/day or higher. The absence of these lesions at 0.14 mg/kg/day, in which there was tachycardia without significant hypotension, indicated that hypotension may be important for the development of cardiovascular lesions.
The threshold dose/serum concentrations of minoxidil for hemodynamic effects (heart rate) and cardiovascular toxicity were approximately 0.05 mg/kg/day (2.0 ng/mL) and 0.14 mg/kg/day (7.96 ng/mL), respectively.
Since dogs are particularly sensitive to the cardiac effects of minoxidil and other vasodilating agents, they are not considered to accurately predict human risk for these compounds. Human exposure would be about 0.028 mg/kg/day (assuming a 60 kg individual using twice daily applications of 1 mL of 5% minoxidil topical solution and a mean level of minoxidil absorption in humans of 1.7%), which provides a difference in exposure between humans and dogs of 8-fold or more for a 5% solution. There is no clinical or autopsy evidence that orally administered minoxidil causes similar cardiac toxicity in humans.
Drug Interaction Studies: There was no evidence of alteration in toxicity when minoxidil was given concomitantly with (a) hydrochlorothiazide and propranolol in rats and monkeys for up to 1 month, and (b) furosemide and digoxin in rats for 1 month. Hydrochlorothiazide partially reduced increases in heart weight and total body exchangeable sodium produced by minoxidil in a 1-month monkey study.
Longer term treatment in rats, dogs and monkeys showed cardiac hypertrophy and cardiac dilation (in rats). Hydrochlorothiazide partly reversed the increased heart weight in monkeys.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. Men’s ROGAINE (Minoxidil Topical Solution 20 mg/mL (2% w/v)), Men’s ROGAINE® FOAM 5% (Aerosol Foam, 50 mg/g (5% w/w)), Women’s ROGAINE® FOAM 5% (Minoxidil Foam 50 mg/g (5%w/w)) Submission Control # 303497, Product Monograph, Kenvue Canada Inc. (December 24, 2025)
- 2. Men's Gln-Minoxidil (Aerosol Foam, 50 mg/g (5% w/w)), Submission Control # 304626, Product Monograph, Glenmark Pharmaceuticals Canada Inc. (April 2, 2026)..