


Product Monograph - Rosiver
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Topical | Cream / 1% | Cetyl alcohol, stearyl alcohol, methyl parahydroxybenzoate (methyl paraben), propyl parahydroxybenzoate (propyl paraben), propylene glycol. For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
ROSIVER (ivermectin) Cream, 1% is indicated for the topical treatment of inflammatory lesions (papules and pustules) of rosacea in adults 18 years of age or older.
Geriatrics (≥ 65 years of age):
Approximately 300 subjects aged 65 years and older were treated over all clinical trials with ROSIVER. In pivotal trials, efficacy and safety in subjects ≥ 65 years of age were found to be comparable to that in adults less than 65 years of age.
Pediatrics (< 18 years of age):
Safety and effectiveness in pediatric patients have not been established.
CONTRAINDICATIONS
ROSIVER (ivermectin) Cream, 1% is contraindicated in:
- Patients who are hypersensitive to this drug or to any ingredient in the formulation or component of the container. For a complete listing, see DOSAGE FORMS, COMPOSITION AND PACKAGING.
WARNINGS AND PRECAUTIONS
General
Patients may experience aggravation of rosacea. In case of severe worsening, the treatment should be discontinued.
The medicinal product contains:
•Cetyl alcohol and stearyl alcohol, which may cause local skin reactions (eg. contact dermatitis),
•Methyl parahydroxybenzoate (methyl paraben) and propyl parahydroxybenzoate (propyl paraben), which may cause allergic reactions (possibly delayed),
•Propylene glycol, which may cause skin irritation.
Interactions with known irritants or photo-enhancers have not been studied. Concomitant use of potentially irritating topical products or procedures should be avoided.
Immune
Photosafety and sensitization potential were not specifically evaluated in humans. Dermal studies in guinea pigs produced evidence of probable delayed sensitization and possible photoallergenicity. See TOXICOLOGY.
Special Populations
Pregnant Women: There are no adequate and well-controlled studies from the topical use of ivermectin in pregnant women. ROSIVER (ivermectin) Cream, 1% should not be used during pregnancy unless the potential benefit to the mother justifies the potential risk to the fetus.
Reproductive toxicity studies have shown that ivermectin administered orally is teratogenic in rats and rabbits. See TOXICOLOGY
Nursing Women: Following oral ivermectin administration, ivermectin is excreted in human milk, (milk concentrations were 0.37-fold of those measured in plasma (37.9 ± 0.54 ng/mL) following an oral dose of 150 µg/kg).
Excretion in human milk following topical administration has not been evaluated. In oral studies in rats, ivermectin was excreted in the milk of dams at about 4-fold the maternal plasma concentrations; ivermectin related toxic central nervous system, physical and behavioral development effects and mortality were observed in the litters, which were attributed to the low p-glycoprotein activity of the blood-brain barrier of the rat pups.
Due to the potential for serious adverse reactions from ROSIVER in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
During clinical trials, 2047 subjects with inflammatory lesions of rosacea received ROSIVER once daily. A total of 1555 subjects were treated once daily for at least 12 weeks, and 519 subjects were treated for approximately one year.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse drug reactions, reported in ≥ 0.1% and ≤ 1% of subjects treated with ROSIVER for at least 3 months in vehicle-controlled clinical trials, are shown in Table 1 below:
| Table 1: Adverse Drug Reactions Reported in Controlled Clinical Trials | |||||
| System Organ Class / Preferred Term | ROSIVER n= 910 (%) | Vehicle n= 461 (%) | |||
| Skin and subcutaneous tissue disorders | 62 (6.8%) | 49 (10.6%) | |||
| Skin burning sensation | 9 (1.0) | 10 (2.2) | |||
| Skin irritation | 8 (0.9) | 11 (2.4) | |||
| Pruritis | 7 (0.8) | 5 (1.1) | |||
| Dry skin | 5 (0.5) | 3 (0.7) | |||
The safety profile remained stable under conditions of long-term use as observed in long-term treatment for up to one year.
Post-market Adverse Reactions
Skin and Subcutaneous Tissue Disorders: Application site erythema, dermatitis contact (allergic or irritant), rosacea aggravated, swelling face.
Hepatobiliary Disorder: Transaminase increased.
DRUG INTERACTIONS
Overview
No clinical drug interaction studies have been conducted with ROSIVER (ivermectin) Cream, 1%.
Ivermectin is a known substrate of p-glycoprotein.
In vitro studies have shown that ivermectin, at ROSIVER therapeutic systemic concentrations, neither inhibits nor induces cytochrome P450 (CYP450) enzymes. Based on these results, there is no potential for clinically relevant systemic drug-drug interactions between ivermectin and other drugs under the conditions of topical use of Ivermectin 1% Cream.
Interactions with known irritants or photo-enhancers have not been studied.
DOSAGE AND ADMINISTRATION
Dosing Considerations
Hands should be washed after applying ROSIVER.
Cosmetics may be applied after ROSIVER has dried.
ROSIVER is not for oral, ophthalmic, or intravaginal use.
Recommended Dose and Dosage Adjustment
Once daily application of five pea-sized amounts (one to each of the five areas of the face: forehead, chin, nose, each cheek) per day.
Administration
Apply ROSIVER once daily at bedtime. Use a pea-size amount for each area of the face: forehead, chin, nose, each cheek.
Spread as a thin layer across the entire face, avoiding the eyes and lips.
OVERDOSAGE
For management of a suspected drug overdose, contact your regional Poison Control Centre.
There are no reports of overdosage with ROSIVER (ivermectin) Cream, 1%.
In cases of accidental or significant exposure to unknown quantities of veterinary formulations of ivermectin in humans, either by ingestion, inhalation, injection, or exposure to body surfaces, the following adverse effects have been reported most frequently: rash, edema, headache, dizziness, asthenia, nausea, vomiting, and diarrhea. Other adverse effects that have been reported include: seizure, ataxia, dyspnea, abdominal pain, paresthesia, urticaria, and contact dermatitis.
In case of accidental ingestion, supportive therapy, if indicated, should include parenteral fluids and electrolytes, respiratory support (oxygen and mechanical ventilation if necessary) and pressor agents if clinically significant hypotension is present. Ivermectin is largely excreted via the feces, and therefore prompt gastrointestinal decontamination (induced emesis and gastric lavage with airway secured) followed by the administration of activated charcoal may be helpful.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
The mechanism of action of ROSIVER in treating rosacea is unknown.
Pharmacodynamics
Anti-inflammatory properties of topical ivermectin have been observed in animal models of skin inflammation.
Ivermectin is known to have endectocidal properties via selective high affinity binding to glutamate-gated anion channels and γ-aminobutyric acid-gated chloride channels. These channels occur in peripheral motor synapses of parasites, but occur only in the central nervous system in mammals. Ivermectin is normally excluded from the mammalian central nervous system by mature levels of p-glycoprotein activity
See DETAILED PHARMACOLOGY.
Pharmacokinetics
Absorption: The absorption of ivermectin from ROSIVER was evaluated in a clinical trial in adult subjects with severe papulopustular rosacea, under maximal use conditions. At steady state (after 2 weeks of treatment), the highest mean (± standard deviation) plasma concentrations of ivermectin peaked within 10 ± 8 hours post-dose (Cmax: 2.10 ± 1.04 ng/mL range: 0.69 - 4.02 ng/mL) and the highest mean (± standard deviation) AUC0-24hr was 36.14 ± 15.56 ng.hr/mL (range: 13.69-75.16 ng.hr/mL). In addition, systemic exposure assessment in longer treatment duration (Phase 3 studies) evidenced that there was no plasma accumulation of ivermectin over the 52-week treatment period. These levels obtained under steady-state conditions are lower than those observed following oral administration of ivermectin
Distribution: An in vitro penetration study in excised human skin demonstrated that after topical application of ivermectin 1% cream, the penetrated dose represented approximately 2% of the applied dose (1.59% in stratum corneum, 0.55% in epidermis plus dermis and 0.03% in receptor fluid).
Ivermectin is greater than 99% bound to human plasma proteins (99.5% to human serum albumin) without significant binding to erythrocytes, based on in vitro studies.
Human fetal transfer of ivermectin has not been studied, however following oral administration to pregnant rats, the fetuses are exposed to ivermectin and/or its metabolites.
Ivermectin is a known substrate of P-glycoprotein.
Following oral administration, ivermectin is excreted in human milk. Milk concentrations were 0.37-fold of those measured in maternal plasma following an oral dose of 150 µg/kg (14.13 ± 0.43 ng/mL in milk; 37.9 ± 0.54 ng/mL in plasma).
Metabolism: Ivermectin is metabolized in the liver. In vitro studies using human hepatic microsomes and recombinant CYP450 enzymes have shown that ivermectin is primarily metabolized by CYP3A4 into three metabolites.
In vitro studies show that ivermectin, at ROSIVER therapeutic systemic concentrations, does not inhibit the CYP450 isoenzymes 1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 3A4, 4A11 or 2E1, and does not induce CYP450 enzyme expression (1A2, 2B6, 2C9 or 3A4).
Two major metabolites of ivermectin were identified in a maximal use topical, clinical pharmacokinetic study (3’’-O-demethyl ivermectin and 4a-hydroxy ivermectin). Similar to the parent compound, metabolites reached steady state conditions by 2 weeks of treatment, with no evidence of accumulation up to 12 weeks.
Excretion: In humans, ivermectin and its metabolites were excreted almost exclusively in feces, with less than 1% of the administered dose excreted in urine. Terminal plasma ivermectin half-life averaged 6 days (mean: 145 hours, range 92-238 hours) in patients receiving a once daily cutaneous application of ROSIVER for 28 days, in the maximal use, clinical pharmacokinetic study.
Special Populations and Conditions
Studies to assess the effect of ROSIVER in special populations were not conducted. The very low systemic exposures observed in clinical studies indicate that no new safety issues would be anticipated for ROSIVER in special patient populations.
STORAGE AND STABILITY
Store at room temperature (15°C to 25°C).
SPECIAL HANDLING INSTRUCTIONS
Hands should be washed immediately after applying ROSIVER (ivermectin) Cream, 1%. Access to ROSIVER by children or pets should be prevented during usage, disposal and storage of the product.
DOSAGE FORMS, COMPOSITION AND PACKAGING
ROSIVER (ivermectin) Cream, 1% w/w (10 mg/g) is a white to pale yellow hydrophilic cream (oil-in-water emulsion) and is supplied in a 15 g, 30 g, 45 g and 60 g laminated tubes* with a child-resistant cap. Physician samples are supplied in 2 g laminate tubes with a non-child-resistant cap.
* Not all pack sizes currently marketed in Canada.
Medicinal ingredient: Ivermectin
Non medicinal ingredients:
Carbomer copolymer (type B), Cetyl alcohol, Citric acid monohydrate, Dimeticone (20 Cst), Disodium edetate, Glycerol, Isopropyl palmitate, Macrogol cetostearyl ether, Methyl parahydroxybenzoate, Oleyl alcohol, Phenoxyethanol, Propylene glycol, Propyl parahydroxybenzoate, Purified water, Sodium hydroxide 10% w/w aqueous solution, Sorbitan stearate(Type 1), Stearyl alcohol
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Ivermectin
Chemical name: Ivermectin is a mixture of component H2B1a and H2B1b
Component H2B1a:
5-O-demethyl-22,23-dihydroavermectin A1a
Component H2B1b:
5-O-demethyl-25-de(1-methylpropyl)-25-(1-methylethyl)-22,23-dihydroavermectin A1a
Molecular formula and (molecular mass): Component H2B1a: C48H74O14 (875) Component H2B1b: C47H72O14 (861)
Structural formula:
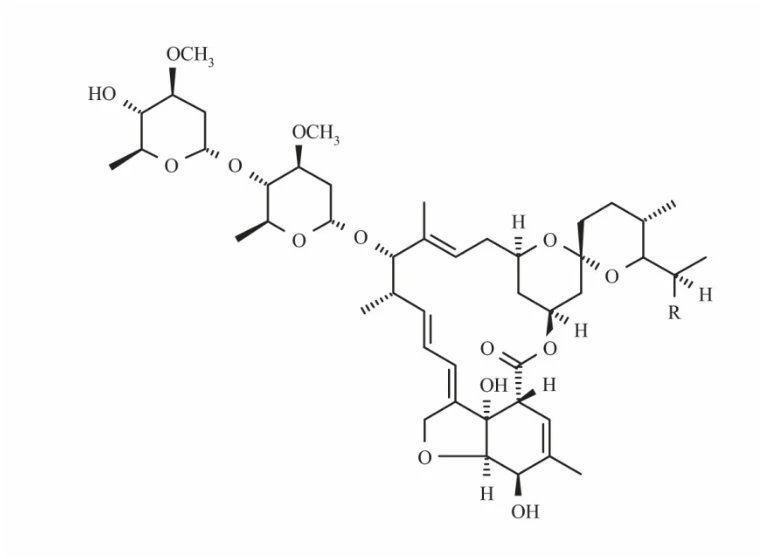
Component H2B1a: R = C2H5, Component H2B1b: R = CH3.
Physicochemical properties: Ivermectin is a white or yellowish-white, crystalline powder, slightly hygroscopic. Practically insoluble in water, freely soluble in methylene chloride and soluble in ethanol (96%).
CLINICAL TRIALS
ROSIVER (ivermectin) Cream, 1% applied once daily at bedtime was evaluated in the treatment of inflammatory lesions of rosacea in two pivotal randomized, double-blind, vehicle-controlled clinical trials, which were identical in design.
Study demographics and trial design
| Table 2 - Summary of patient demographics | |||||
| Study | Trial design | Dosage, route of administration and duration | Study subjects, N | Mean age (Range) | Gender, N |
| Study 1 | Multicenter, randomized, double-blind, parallel-group, vehicle-controlled | Ivermectin 1% Cream once daily Ivermectin Cream Vehicle once daily Once daily Topical (facial application) 12 weeks | 683 | 50.4 (19-88) | Male, 217 Female, 466 |
| Study 2 | Multicenter, randomized, double-blind, parallel-group, vehicle-controlled | Ivermectin 1% Cream once daily CD5024 Cream Vehicle once daily Topical (facial application) 12 weeks | 688 | 50.2 (18-89) | Male, 229 Female, 459 |
Results
The co-primary efficacy endpoints in both pivotal trials were the success rate based on the IGA outcome (percentage of subjects “clear” and “almost clear” at Week 12 of the study) and absolute change from baseline in inflammatory lesion counts. The IGA scale is based on the following definitions:
| Grade | Score | Clinical Description |
| Clear | 0 | No inflammatory lesions present, no erythema |
| Almost Clear | 1 | Very few small papules/pustules, very mild erythema |
| Mild | 2 | Few small papules/pustules, mild erythema |
| Moderate | 3 | Several small or large papules/pustules, moderate erythema |
| Severe | 4 | Numerous small and/or large papules/pustules, severe erythema |
Using the 5-point Investigator Global Assessment (IGA) scale, 79% of subjects were scored as moderate (IGA=3) and 21% scored as severe (IGA= 4) at baseline.
The following table presents efficacy outcomes from both pivotal studies.
| Table 3 - Results of Phase III pivotal studies | |||||||||||||||||
| Study 1 | Study 2 | ||||||||||||||||
ROSIVER (N=451) | Vehicle (N=232) | ROSIVER (N=459) | Vehicle (N=229) | ||||||||||||||
| Investigator Global Assessment | |||||||||||||||||
| Number (%) of Subjects Clear or Almost Clear in the IGA at Week 12 | 173 (38.4) | 27 (11.6) | 184 (40.1) | 43 (18.8) | |||||||||||||
| Inflammatory Lesions | |||||||||||||||||
Mean Inflammatory Lesion Count at Baseline | 31.0 | 30.5 | 33.3 | 32.2 | |||||||||||||
Mean Inflammatory Lesion Count at Week 12 | 10.6 | 18.5 | 11.0 | 18.8 | |||||||||||||
Mean Absolute Change (% Change) in Inflammatory Lesion Count from Baseline at Week 12 | -20.5 (-64.9) | -12.0 (-41.6) | -22.2 (-65.7) | -13.4 (-43.4) | |||||||||||||
| p-value | <0.001 | - | <0.001 | - | |||||||||||||
The results from both pivotal clinical studies demonstrated that ROSIVER applied once daily for 12 weeks was statistically more effective than vehicle cream in terms of IGA success rate and absolute change in inflammatory lesion counts (p<0.001).
Starting from 4 weeks of treatment, ROSIVER was significantly more effective than vehicle cream for both the co-primary efficacy endpoints (p<0.05).
IGA was assessed during the 40-week investigator-blinded extension of the two pivotal studies and the percentages of subjects treated with ROSIVER achieving an IGA score of 0 (“clear”) or 1 (“almost clear”) continued to increase up to Week 52. The Success Rate (IGA = 0 or 1) at Week 52 was 71% and 76% in Studies 1 and 2, respectively.
The efficacy and safety of ROSIVER in the treatment of inflammatory lesions of rosacea were also evaluated in another supportive randomized, investigator-blinded, active-controlled clinical study. The study was conducted in 962 subjects aged 18 years and older who were treated for 16 weeks with either ROSIVER once daily or Metronidazole 0.75% w/w cream twice daily. In this study, 99.7% of subjects were Caucasian and 65.2% were female; on the IGA scale, 83.3% of subjects were scored as moderate (IGA=3) and 16.7% scored as severe (IGA=4) at baseline.
The results of the study demonstrated that ROSIVER was statistically more effective than Metronidazole 7.5 mg/g cream on the primary efficacy endpoint (Mean Percent Change in Inflammatory Lesion Counts) with a reduction of 83.0% and 73.7% from baseline after 16 weeks of treatment for the ivermectin and metronidazole groups respectively (p<0.001). The superiority of ROSIVER at Week 16 was confirmed by the Success Rate based on IGA and Absolute Change in Inflammatory Lesion Counts (secondary endpoints (p<0.001)).
DETAILED PHARMACOLOGY
Primary pharmacodynamics
The mechanism of action of ivermectin in ROSIVER in treating rosacea is unknown.
Secondary pharmacodynamics
Animal Models of inflammation:
In mouse ear edema models, topical ivermectin treatment showed anti-inflammatory activities (dose-dependent reduction of ear edema, reduction of tumor necrosis factor alpha). In a mouse model of allergen-induced atopic dermatitis, topical application of ivermectin reduced all inflammation symptoms including ear edema, epidermal thickness, skin eosinophil peroxidase, skin mastocyte count, and serum IgE content. The pharmacological activity of the 2 major human ivermectin metabolites has not been studied.
MICROBIOLOGY
Microbiological activity was not specifically studied in the development of ROSIVER.
Ivermectin is known to bind selectively to specific neurotransmitter receptors that function in the peripheral motor synapses of parasites, producing an endectocidal effect in nematodes, arthropods and insects.
TOXICOLOGY
General Toxicology:
Repeat-dose dermal application studies of ivermectin 1% cream in minipigs did not show systemic toxic effects or local toxicity. The exposure in minipigs via dermal application at the highest dose given in the study was comparable to the systemic exposure in humans at the therapeutic dose of ROSIVER.
Genotoxicity:
Ivermectin was not mutagenic in vitro in bacterial and photo-bacterial reverse mutation assays, in the mouse lymphoma assay, and in vivo in the oral micronucleus test in rats.
Carcinogenicity:
Chronic (1 year) repeated topical application of ROSIVER enhanced simulated solar ultraviolet radiation-induced non-melanoma skin carcinogenesis in albino Skh HR-1 hairless mouse (tumour potency factor in both sexes combined was 1.69; 1.74 in male mice and 1.51 in female mice - compared with an expected no adverse effect tumour potency factor of 1.00). Increased incidence of skin irritation induced by both the vehicle cream and by ROSIVER cream in this study is very likely to be the cause for increased incidence of UV radiation-induced skin tumors in these groups, when compared to mice only exposed to UV radiation.
In a 2-year topical carcinogenicity study in mice (without simulated solar light exposure), ROSIVER was not tumorigenic when applied daily at doses corresponding to up to 10 mg/kg/day of ivermectin. At this dose, the plasma AUC in mice was 645.54 (m)/352 (f) times the human plasma AUC associated with the maximum recommended topical use of ROSIVER.
In a 2-year oral carcinogenicity study in rats, ivermectin was considered not tumorigenic when administered daily at doses up to 3 mg/kg/day. At this dose, the plasma exposure of animals represented at least 282 times the human plasma AUC associated with the maximum recommended topical use of ROSIVER. An increase in the incidence of benign hepatocellular adenomas and related hepatic pre-neoplastic changes was reported in males only (at a 9mg/kg/day ivermectin oral dose [832 times the human plasma AUC associated with the maximum recommended topical use of ROSIVER]). There was also a higher incidence of pancreatic benign islet cell adenomas in males, and islet cell carcinoma with no evidence of distant metastasis in females. These neoplastic changes in rodents are not currently considered to be relevant to humans.
Reproductive and Developmental Toxicology:
Ivermectin was found to have no effect on the fertility of male and female rats at oral doses up to 9 mg/kg/day (animal:human AUC ratio ≈ 484).
Teratology studies in the rabbit demonstrated maternal toxicity and carpal flexures in the fetus at an oral ivermectin dose of 4.5mg/kg/day. The NOAEL was established at 3.5 mg/kg/day, a dose corresponding to plasma levels 68 times higher than those obtained at the maximum recommended human dose by topical route (1g application of ROSIVER once daily).
In the rat, cleft palates were observed at the oral ivermectin dose of 12 mg/kg/day. The dose of 4 mg/kg/day was the NOAEL for maternal toxicity and embryofetal development, a dose corresponding to plasma levels 334 times higher than those obtained at the maximum recommended human dose by topical route (1g application of ROSIVER once daily).
The neonatal toxicity in oral rat studies was not related to in-utero exposure, but to postnatal exposure through maternal milk which resulted in high levels of ivermectin in the brain and in plasma of offspring.
Special Toxicology Studies:
Local tolerance studies in rabbits showed that ivermectin 1% cream is irritant on the skin and non-irritant in the eye. Guinea pig studies showed that ivermectin 1% cream is a potential sensitizer and photosensitizer (as is the vehicle cream). Ivermectin 1% cream is not phototoxic following a single topical application followed by ultraviolet radiation.
REFERENCES
- 1. Stein Gold L, Kircik L, Fowler J, Tan J, Draelos Z, Fleischer A, Appell M, Steinhoff M, Lynde C, Liu H, Jacovella J. Efficacy and Safety of Ivermectin 1% Cream in Treatment of Papulopustular Rosacea: Results of Two Randomized, Double-Blind, Vehicle-Controlled Pivotal Studies J Drugs Dermatol. 2014; 13(3): 316-323.
- 2. Stein Gold L, Kircik L, Fowler J, Mark Jackson J, Tan J, Draelos Z, Fleischer A, Appell M, Steinhoff M, Lynde C, Sugarman J, Liu H, and Jacovella J Long-Term Safety of Ivermectin 1% Cream vs Azelaic Acid 15% Gel in Treating Inflammatory Lesions of Rosacea: Results of Two 40-Week Controlled, Investigator-Blinded Trials. J Drugs Dermatol. 2014; 13(11): 1380-1386.