


Product Monograph - Mint-Rivaroxaban
RECENT MAJOR LABEL CHANGES
| 7 WARNINGS AND PRECAUTIONS, Bleeding | 10/2024 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Anticoagulant-Related Nephropathy | 10/2024 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ...................................................................... 4
1 INDICATIONS ............................................................................................................... 4
1.1 Pediatrics ................................................................................................................ 4
1.2 Geriatrics ................................................................................................................ 4
2 CONTRAINDICATIONS ................................................................................................. 4
4 DOSAGE AND ADMINISTRATION ................................................................................. 5
4.1 Dosing Considerations ............................................................................................ 5
4.2 Recommended Dose and Dosage Adjustment ....................................................... 6
4.4 Administration ...................................................................................................... 10
4.5 Missed Dose ......................................................................................................... 10
5 OVERDOSAGE ............................................................................................................ 10
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ............................... 12
7 WARNINGS AND PRECAUTIONS ................................................................................ 12
7.1 Special Populations............................................................................................... 18
7.1.1 Pregnant Women ........................................................................................... 18
7.1.2 Breast-feeding ................................................................................................ 18
7.1.3 Pediatrics ........................................................................................................ 18
7.1.4 Geriatrics ........................................................................................................ 18
8 ADVERSE REACTIONS ................................................................................................ 19
8.1 Adverse Reaction Overview .................................................................................. 19
8.2 Clinical Trial Adverse Reactions ............................................................................ 23
8.3 Less Common Clinical Trial Adverse Reactions ..................................................... 28
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other
Quantitative Data ........................................................................................................... 30
8.5 Post-Market Adverse Reactions ........................................................................... 30
9 DRUG INTERACTIONS ................................................................................................ 30
9.2 Drug Interactions Overview .................................................................................. 30
9.4 Drug-Drug Interactions ......................................................................................... 31
9.5 Drug-Food Interactions ......................................................................................... 35
9.6 Drug-Herb Interactions ......................................................................................... 35
9.7 Drug-Laboratory Test Interactions ........................................................................ 36
10 CLINICAL PHARMACOLOGY ....................................................................................... 36
10.1 Mechanism of Action ...................................................................................... 36
10.2 Pharmacodynamics ........................................................................................ 36
10.3 Pharmacokinetics ........................................................................................... 39
11 STORAGE, STABILITY AND DISPOSAL ......................................................................... 45
12 SPECIAL HANDLING INSTRUCTIONS ........................................................................... 45
PART II: SCIENTIFIC INFORMATION ....................................................................................... 46
13 PHARMACEUTICAL INFORMATION ............................................................................ 46
14 CLINICAL TRIALS ........................................................................................................ 47
14.1 Clinical Trials by Indication ............................................................................. 47
14.2 Comparative Bioavailability Studies ................................................................ 74
15 MICROBIOLOGY ........................................................................................................ 76
16 NON-CLINICAL TOXICOLOGY ..................................................................................... 76
17 SUPPORTING PRODUCT MONOGRAPHS .................................................................... 77
PATIENT MEDICATION INFORMATION .................................................................................. 78
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
MINT-RIVAROXABAN (rivaroxaban) film-coated tablet (10 mg, 15 mg, 20 mg) is indicated for the:
- prevention of venous thromboembolic events (VTE) in patients who have undergone elective total hip replacement (THR) or total knee replacement (TKR) surgery.
- treatment of venous thromboembolic events (deep vein thrombosis [DVT], pulmonary embolism [PE]) and prevention of recurrent DVT and PE.
- prevention of stroke and systemic embolism in patients with atrial fibrillation, in whom anticoagulation is appropriate.
Acute Pulmonary Embolus in haemodynamically unstable patients, or in those requiring thrombolysis or pulmonary embolectomy
For the treatment of VTE, MINT-RIVAROXABAN is not recommended as an alternative to unfractionated heparin in patients with pulmonary embolus who are haemodynamically unstable, or who may receive thrombolysis or pulmonary embolectomy, since the safety and efficacy of rivaroxaban have not been established in these clinical situations (see 4 DOSAGE AND ADMINISTRATION).
1.1 Pediatrics
Pediatrics (< 18 years of age): MINT-RIVAROXABAN is not indicated in children less than 18 years of age.
1.2 Geriatrics
Geriatrics (>65 years of age): Clinical studies have included patients with an age > 65 years (see 7 WARNINGS AND PRECAUTIONS – 7.14 Geriatrics and Renal Impairment, and 4 DOSAGE AND ADMINISTRATION – Renal Impairment and Geriatrics (>65 years of age)).
Safety and efficacy data are available (see 14 CLINICAL TRIALS).
2 CONTRAINDICATIONS
- Clinically significant active bleeding, including gastrointestinal bleeding
- Lesions or conditions at increased risk of clinically significant bleeding, e.g., recent cerebral infarction (hemorrhagic or ischemic), active peptic ulcer disease with recent bleeding, patients with spontaneous or acquired impairment of hemostasis
- Concomitant systemic treatment with strong inhibitors of both CYP 3A4 and P-glycoprotein (P-gp), such as cobicistat, ketoconazole, itraconazole, posaconazole, or ritonavir (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions)
Concomitant treatment with any other anticoagulant, including
- unfractionated heparin (UFH), except at doses used to maintain a patent central venous or arterial catheter,
- low molecular weight heparins (LMWH), such as enoxaparin and dalteparin,
- heparin derivatives, such as fondaparinux, and
- oral anticoagulants, such as warfarin, dabigatran, apixaban, edoxaban, except under circumstances of switching therapy to or from MINT-RIVAROXABAN.
- Hepatic disease (including Child-Pugh Class B and C) associated with coagulopathy, and having clinically relevant bleeding risk (see 7 WARNINGS AND PRECAUTIONS – Hepatic Impairment)
- Pregnancy (see 7 WARNINGS AND PRECAUTIONS – Special Populations, 7.1.1 Pregnant Women)
- Nursing women (see 7 WARNINGS AND PRECAUTIONS – Special Populations,7.1.2 Breast-feeding)
- Hypersensitivity to MINT-RIVAROXABAN (rivaroxaban) or to any ingredient in the formulation, (see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING).
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
As for any non-vitamin K antagonist oral anticoagulant (NOAC) drug, before initiating MINT-RIVAROXABAN (rivaroxaban), ensure that the patient understands and is prepared to accept adherence to NOAC therapy, as directed.
Determine estimated creatinine clearance (eCrCl) in all patients before instituting MINT-RIVAROXABAN (rivaroxaban), and monitor renal function during MINT-RIVAROXABAN treatment, as clinically appropriate. Determination of renal function by eCrCl should occur at least once per year, and especially during circumstances when renal function may be expected to be compromised, i.e., acute myocardial infarction (AMI), acute decompensated heart failure (AHF), increased use of diuretics, dehydration, hypovolemia, etc. Clinically relevant deterioration of renal function may require dosage adjustment or discontinuation of MINT-RIVAROXABAN (see below, Renal Impairment).
Glomerular filtration rate may be estimated by calculating eCrCl, using the Cockroft-Gault formula:
eCrCl (mL/min)=
in males: (140-age) (years) x weight (kg) x 1.23 or, _(140-age) (yrs) x weight (kg) serum creatinine (µmol/L) 72 x serum creatinine (mg/100 mL)
in females: (140-age) (years) x weight (kg) x 1.04 or, (140-age) (yrs) x weight (kg) x 0.85 serum creatinine (µmol/L) 72 x serum creatinine (mg/100 mL)
Switching from Parenteral Anticoagulants to MINT-RIVAROXABAN
MINT-RIVAROXABAN can be started when the infusion of full-dose intravenous heparin is stopped or 0 to 2 hours before the next scheduled injection of full-dose subcutaneous low-molecular-weight heparin (LMWH) or fondaparinux. In patients receiving prophylactic heparin, LMWH or fondaparinux, MINT-RIVAROXABAN can be started 6 or more hours after the last prophylactic dose.
Switching from MINT-RIVAROXABAN to Parenteral Anticoagulants
Discontinue MINT-RIVAROXABAN and give the first dose of parenteral anticoagulant at the time that the next MINT-RIVAROXABAN dose was scheduled to be taken.
Switching from Vitamin K Antagonists (VKA) to MINT-RIVAROXABAN
To switch from a VKA to MINT-RIVAROXABAN, stop the VKA and determine the INR. If the INR is ≤ 2.5, start MINT-RIVAROXABAN at the usual dose. If the INR is > 2.5, delay the start of MINT-RIVAROXABAN until the INR is ≤ 2.5 (see Considerations for INR Monitoring of VKA Activity during Concomitant MINT-RIVAROXABAN Therapy).
Switching from MINT-RIVAROXABAN to a VKA
As with any short-acting anticoagulant, there is a potential for inadequate anticoagulation when transitioning from rivaroxaban to a VKA. It is important to maintain an adequate level of anticoagulation when transitioning patients from one anticoagulant to another.
MINT-RIVAROXABAN should be continued concurrently with the VKA until the INR is ≥ 2.0. For the first 2 days of the conversion period, the VKA can be given in the usual starting doses without INR testing (see Considerations for INR Monitoring of VKA Activity during Concomitant MINT-RIVAROXABAN Therapy). Thereafter, while on concomitant therapy, the INR should be tested just prior to the next dose of MINT-RIVAROXABAN, as appropriate. MINT-RIVAROXABAN can be discontinued once the INR is > 2.0. Once MINT-RIVAROXABAN is discontinued, INR testing may be done at least 24 hours after the last dose of MINT-RIVAROXABAN and should then reliably reflect the anticoagulant effect of the VKA.
Considerations for INR Monitoring of VKA Activity during Concomitant MINT-RIVAROXABAN Therapy
In general, after starting VKA therapy, the initial anticoagulant effect is not readily apparent for at least 2 days, while the full therapeutic effect is achieved in 5-7 days. Consequently, INR monitoring in the first 2 days after starting a VKA is rarely necessary. Likewise, the INR may remain increased for a number of days after stopping VKA therapy.
Although rivaroxaban therapy will lead to an elevated INR, depending on the timing of the measurement (see 10.2 Pharmacodynamics), the INR is not a valid measure to assess the anticoagulant activity of MINT-RIVAROXABAN. The INR is only calibrated and validated for VKA and should not be used for any other anticoagulant, including MINT-RIVAROXABAN.
When switching patients from MINT-RIVAROXABAN to a VKA, the INR should only be used to assess the anticoagulant effect of the VKA, and not that of MINT-RIVAROXABAN. Therefore, while patients are concurrently receiving MINT-RIVAROXABAN and VKA therapy, if the INR is to be tested, it should not be before 24 hours after the previous dose of MINT-RIVAROXABAN and should be just prior to the next dose of MINT-RIVAROXABAN, since at this time the remaining rivaroxaban concentration in the circulation is too low to have a clinically important effect on the INR. If INR testing is done earlier than just prior to the next dose of MINT-RIVAROXABAN, the reported INR will not reflect the anticoagulation effect of the VKA only, because rivaroxaban use may also affect the INR, leading to aberrant readings (see 10.2 Pharmacodynamics).
4.2 Recommended Dose and Dosage Adjustment
Prevention of VTE after THR or TKR
The recommended dose is one 10 mg tablet once daily. MINT-RIVAROXABAN 10 mg may be taken with or without food. The initial dose should be taken within 6 to 10 hours after surgery, provided that hemostasis has been established. If hemostasis is not established, treatment should be delayed.
The duration of administration depends on the type of surgery:
- After elective THR surgery, patients should be administered MINT-RIVAROXABAN for 35 days.
- After elective TKR surgery, patients should be administered MINT-RIVAROXABAN for 14 days.
Treatment of VTE and Prevention of recurrent DVT and PE
MINT-RIVAROXABAN is NOT recommended as an alternative to unfractionated heparin in patients with acute pulmonary embolus who are hemodynamically unstable, or who may receive thrombolysis or pulmonary embolectomy, since the safety and efficacy of rivaroxaban have not been established in these clinical situations (see 1 INDICATIONS).
The recommended dose for the initial treatment of acute DVT or PE is 15 mg twice daily (one tablet in the morning and one in the evening) for the first 3 weeks followed by 20 mg once daily for the continued treatment and prevention of recurrent DVT and PE.
Short duration of therapy (at least 3 months) should be considered in patients with DVT or PE provoked by major transient risk factors (e.g. recent major surgery or trauma). The duration of therapy should be individualised after careful assessment of the treatment benefit against the risk for bleeding.
Following completion of at least 6 months treatment for DVT or PE, the recommended dose for prevention of recurrent DVT and PE is 20 mg or 10mg once daily based on an individual assessment of the risk of recurrent DVT and PE against the risk for bleeding. For example, in patients in whom the risk of recurrent DVT or PE is considered high, such as those with complicated comorbidities who are at high risk of VTE recurrence, a dose of 20mg should be considered.
Longer duration of therapy should be considered in patients with DVT or PE provoked by permanent risk factors, unprovoked DVT or PE, or a history of recurrent DVT or PE.
The recommended maximum daily dose is 30 mg during the first 3 weeks of treatment and 20 mg thereafter.
MINT-RIVAROXABAN 15 mg and 20 mg tablets should be taken with food. MINT-RIVAROXABAN 10 mg tablets may be taken with or without food.
Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation
The recommended dose is one 20 mg tablet of MINT-RIVAROXABAN taken once daily with food (see 10.3 Pharmacokinetics, Absorption).
For patients with moderate renal impairment (CrCl 30 – 49 mL/min), the recommended dose is 15 mg once daily with food (see Renal Impairment below).
The recommended maximum daily dose is 20 mg.
Acute myocardial infarction (AMI): Consideration should be given to discontinuing MINT-RIVAROXABAN in the setting of acute myocardial infarction should the treatment of myocardial infarction involve invasive procedures, such as percutaneous coronary revascularization, or coronary artery bypass surgery. Similar consideration should be given if thrombolytic therapy is to be initiated, because bleeding risk may increase. Patients with acute myocardial infarction should be treated according to current clinical guidelines. In this setting, MINT-RIVAROXABAN may be resumed, when deemed clinically appropriate, for the prevention of stroke and systemic embolism upon completion of these revascularization procedures.
Concomitant use of ASA or clopidogrel with MINT-RIVAROXABAN in patients with atrial fibrillation increases the risk of bleeding. Concomitant use of ASA or other antiplatelet agents based on medical need to prevent myocardial infarction should be undertaken with caution. Close clinical surveillance is recommended.
Other situations requiring thrombolytic therapy: MINT-RIVAROXABAN should be discontinued in situations such as acute ischemic stroke where current clinical practice calls for administering thrombolytic therapy. MINT-RIVAROXABAN treatment may be subsequently resumed as soon as is deemed clinically appropriate. Measurement of a PT time, in seconds, using the Neoplastin reagent, may inform therapeutic decision-making (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
Concomitant use of MINT-RIVAROXABAN 10 mg, 15 mg and 20 mg with antiplatelet agents: The concomitant use of MINT-RIVAROXABAN with antiplatelet agents increases the risk of bleeding (see 7 WARNINGS AND PRECAUTIONS – Bleeding). If concomitant antiplatelet therapy is contemplated with MINT-RIVAROXABAN 10 mg, 15 mg, and 20 mg, a careful assessment of the potential risks should be made against potential benefits, weighing risk of increased bleeding against expected benefit.
Patients with nonvalvular atrial fibrillation who undergo PCI with stent placement: Patients with nonvalvular atrial fibrillation who undergo PCI with stent placement should receive a reduced dose of 15 mg MINT-RIVAROXABAN once daily (or 10 mg MINT-RIVAROXABAN once daily for patients with moderate renal impairment [CrCl 30 – 49 mL/min]) in combination with a P2Y12 inhibitor (e.g, clopidogrel). This treatment regimen is recommended for a maximum of 12 months after PCI with stent placement (see 10.2 Pharmacodynamics, Patients with nonvalvular atrial fibrillation who undergo PCI with stent placement). After completion of the antiplatelet therapy, rivaroxaban dosage should be changed to the standard dose for patients with atrial fibrillation.
Cardioversion:
Patients can be maintained on MINT-RIVAROXABAN while being cardioverted (see 10.2 Pharmacodynamics, Patients undergoing cardioversion).
Hepatic Impairment
MINT-RIVAROXABAN is contraindicated in patients with hepatic disease (including Child-Pugh Class B and C) associated with coagulopathy and having clinically relevant bleeding risk. Patients with severe hepatic impairment or chronic hepatic disease were excluded from pivotal clinical trials.
The limited clinical data for patients with moderate hepatic impairment indicate a significant increase in the pharmacological activity. MINT-RIVAROXABAN should be used with caution in these patients (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS – Hepatic Impairment, and 10.3 Pharmacokinetics – Hepatic Insufficiency).
The limited data available for patients with mild hepatic impairment without coagulopathy indicate that there is no difference in pharmacodynamic response or pharmacokinetics as compared to healthy subjects.
Renal Impairment
Table 1 - Dosage and Administration for Patients According to Renal Function
Creatinine Clearance (CrCl) Indication | Normal >80 mL/min | Mild 50-80 mL/min | Moderate 30-49 mL/min | Severe* 15 - < 30 mL/min | < 15 mL/min | |||||
|---|---|---|---|---|---|---|---|---|---|---|
| Prevention of VTE After THR or TKR | 10 mg od | 10 mg od | MINT-RIVAROXABAN is not recommended | |||||||
| Treatment of VTE and Prevention of Recurrent DVT and PE | 15 mg bid for 3 weeks, followed by 20 mg od | 15 mg bid for 3 weeks, followed by 20 mg od | ||||||||
Prevention of recurrent DVT and PE following completion of at least 6 months treatment | 10 mg od or 20 mg od | 10 mg od or 20 mg od | ||||||||
| Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation | 20 mg od | 15 mg od | 15 mg od | |||||||
od=once daily, bid=twice daily
*must be used with caution
MINT-RIVAROXABAN should be used with caution in patients receiving other drugs which increase rivaroxaban plasma concentrations. Physicians should consider the benefit/risk of anticoagulant therapy before administering MINT-RIVAROXABAN to patients with moderate renal impairment with a creatinine clearance close to the severe renal impairment category (CrCl < 30 mL/min) or with a potential to have deterioration of renal function during therapy. Renal function should be followed carefully in these patients (see 7 WARNINGS AND PRECAUTIONS – Renal Impairment, and 9.4 Drug-Drug Interactions).
In patients with severe renal impairment (CrCl 15 - < 30 mL/min), rivaroxaban plasma levels may be significantly elevated compared to healthy volunteers (1.6-fold on average) which may lead to an increased bleeding risk. Due to limited clinical data, MINT-RIVAROXABAN must be used with caution in these patients. No clinical data are available for patients with CrCl < 15 mL/min. Use is not recommended in patients with CrCl < 15ml/min. Patients who develop acute renal failure while on MINT-RIVAROXABAN should discontinue such treatment.
Gender, Race, or Body Weight
No dose adjustment is required for gender or race. (see 10.3 Pharmacokinetics –Sex, Ethnic Origin, and Body Weight).
Geriatrics (>65 years of age)
No dose adjustment is generally required for the elderly. Increasing age may be associated with declining renal function (see 7 WARNINGS AND PRECAUTIONS – Renal Impairment, and 4 DOSAGE AND ADMINISTRATION – Renal Impairment).
Pediatrics (<18 years of age)
MINT-RIVAROXABAN is not indicated in children less than 18 years of age.
4.4 Administration
Tablet:
Swallow the tablet with liquid.
MINT-RIVAROXABAN 15 mg and 20 mg tablets should be taken with food (see 10.3 Pharmacokinetics, Absorption).
Administration of Crushed Tablets:
For patients who are unable to swallow whole tablets, MINT-RIVAROXABAN tablets may be crushed and mixed with applesauce immediately prior to use and administered orally. After the administration of a crushed MINT-RIVAROXABAN 15 mg or 20 mg tablet, the dose should be immediately followed by food.
A crushed MINT-RIVAROXABAN tablet may be also administered via nasogastric (NG) tube. After confirming gastric placement of the NG tube, the crushed tablet should be suspended in 50 mL of water and administered via the NG tube after which it should be flushed with water. Because rivaroxaban absorption is dependent on the site of drug release in the GI tract, avoid administration of MINT-RIVAROXABAN distal to the stomach as this can result in reduced absorption and therefore reduced drug exposure. After the administration of a crushed MINT-RIVAROXABAN 15 mg or 20 mg tablet, the dose should then be immediately followed by enteral feeding (10.3 Pharmacokinetics, Absorption).
An in vitro compatibility study indicated that there is no adsorption of rivaroxaban from a water suspension of a crushed rivaroxaban tablet to PVC or silicone nasogastric (NG) tubing.
4.5 Missed Dose
It is essential to adhere to the dosage schedule provided.
MINT-RIVAROXABAN 10 mg, 15 mg, or 20 mg tablets taken once a day:
If a dose is missed, the patient should take MINT-RIVAROXABAN immediately and continue on the following day with the once daily intake as before. A double dose should not be taken to make up for a missed tablet.
MINT-RIVAROXABAN 15 mg taken twice a day:
If a dose is missed during the 15 mg twice daily treatment phase the patient should take the next dose immediately to ensure the intake of 30 mg total dose per day. In this case two 15 mg tablets may be taken at once. The following day the patient should continue with the regular 15 mg twice daily intake schedule as recommended.
5 OVERDOSAGE
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
Overdose following administration of MINT-RIVAROXABAN (rivaroxaban) may lead to hemorrhagic complications due to its pharmacodynamic properties.
In adults, rare cases of overdose up to 600 mg have been reported without bleeding complications or other adverse reactions. There are limited data available in children. No further increase in average plasma exposure is expected due to limited absorption at supratherapeutic doses of 50 mg or above in adults, however, no data are available at supratherapeutic doses in children, because of a solubility ceiling effect.
A specific reversal agent for MINT-RIVAROXABAN is not available. The use of activated charcoal to reduce absorption in case of rivaroxaban overdose may be considered. Administration of activated charcoal up to 8 hours after overdose may reduce the absorption of rivaroxaban.
Due to the high plasma protein binding, rivaroxaban is not expected to be removed by dialysis (see 10.3 Pharmacokinetics, Distribution).
Management of Bleeding
In the event of hemorrhagic complications in a patient receiving MINT-RIVAROXABAN, treatment should be temporarily discontinued, and the source of bleeding investigated. Rivaroxaban has a half-life of approximately 5 to 13 hours in adults (see 10.3 Pharmacokinetics). Consideration should be given to the resumption of antithrombotic therapy when clinically appropriate to adequately control risk of underlying thrombosis.
Management of bleeding should be individualised according to the severity and location of the hemorrhage. Appropriate symptomatic treatment should be used as needed, such as mechanical compression (e.g, for severe epistaxis), surgical hemostasis with bleeding control procedures, fluid replacement and hemodynamic support, blood products (packed red cells or fresh frozen plasma, depending on associated anemia or coagulopathy) or platelets.
If bleeding cannot be controlled by the above measures, consider administration of one of the following procoagulants:
- activated prothrombin complex concentrate (APCC), e.g., FEIBA
- prothrombin complex concentrate (PCC)
- recombinant Factor-VIIa (rFVIIa)
However, there is currently only very limited experience with the use of these products in individuals receiving rivaroxaban.
In a randomized, double-blind, placebo-controlled study, a non-activated prothrombin complex concentrate (PCC) given to 6 healthy male subjects who had previously received rivaroxaban, completely reversed its anticoagulant effect within 15 minutes, based on coagulation tests. Although this study may have important clinical implications, this effect of PCC has not yet been confirmed in patients with active bleeding who have been previously treated with rivaroxaban.
Protamine sulfate and vitamin K are not expected to affect the anticoagulant activity of rivaroxaban. There is limited experience with tranexamic acid and no experience with aminocaproic acid and aprotinin in adults receiving rivaroxaban. There is no experience on the use of these agents in children receiving rivaroxaban. There is neither scientific rationale for benefit or experience with the systemic hemostatic desmopressin in individuals receiving rivaroxaban.
The prothrombin time (PT), measured in seconds, is influenced by rivaroxaban in a dose- dependent way with a close correlation to plasma concentrations if the Neoplastin® reagent is used. In patients who are bleeding, measuring the PT (Neoplastin® reagent) may be useful to assist in determining an excess of anticoagulant activity. INR should NOT be used to assess the anticoagulant effect of MINT-RIVAROXABAN (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests and 10.2
Pharmacodynamics).
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 2 – Dosage Forms, Strengths, Composition and Packaging
10 mg Tablets:
Pink coloured, circular, biconvex, film-coated tablets for oral use, debossed with ‘J 8’ on one side and plain on the other side.
MINT-RIVAROXABAN (rivaroxaban) 10 mg tablets are supplied in HDPE bottles of 30, 50, 90, and 100 tablets.
15 mg Tablets:
Light red coloured, circular, biconvex, film coated tablets for oral use, debossed with ‘J 9’ on one side and plain on the other side.
MINT-RIVAROXABAN tablets 15 mg are supplied in HDPE bottles of 30, 50, 90 and 100 tablets.
20 mg Tablets:
Red coloured, triangular shape, film coated tablets, debossed with 'J 10' on one side and plain on the other side.
MINT-RIVAROXABAN tablets 20 mg are supplied in HDPE bottles of 30, 50, 90 and 100 tablets.
7 WARNINGS AND PRECAUTIONS
General
PREMATURE DISCONTINUATION OF ANY ORAL ANTICOAGULANT, INCLUDING MINT-RIVAROXABAN, INCREASES THE RISK OF THROMBOTIC EVENTS.
To reduce this risk, consider coverage with another anticoagulant if MINT-RIVAROXABAN is discontinued for a reason other than pathological bleeding or completion of a course of therapy.
Bleeding
MINT-RIVAROXABAN, like other anticoagulants, should be used with caution in patients with an increased bleeding risk. Bleeding can occur at any site during therapy with MINT-RIVAROXABAN. The possibility of a hemorrhage should be considered in evaluating the condition of any anticoagulated patient. Any unexplained fall in hemoglobin or blood pressure should lead to a search for a bleeding site. Patients at high risk of bleeding should not be prescribed MINT-RIVAROXABAN (see 2 CONTRAINDICATIONS).
| Route of Administration | Dosage Form / Strength/Composition | Non-medicinal Ingredients |
| Oral | Film-coated tablet, 10 mg, 15 mg and 20 mg rivaroxaban | Cellulose microcrystalline, colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, polyethylene glycol, red iron oxide, sodium lauryl sulphate, and titanium dioxide |
Should severe bleeding occur, treatment with MINT-RIVAROXABAN must be discontinued and the source of bleeding investigated promptly.
Close clinical surveillance (looking for signs of bleeding or anemia) is recommended throughout the treatment period, especially in the presence of multiple risk factors for bleeding (see Table 3 below).
Table 3 - Factors Which Increase Hemorrhagic Risk
| Factors increasing rivaroxaban plasma levels | Severe renal impairment (CrCl < 30 mL/min) |
|---|---|
| Concomitant systemic treatment with strong inhibitors of both CYP 3A4 and P-gp | |
| Pharmacodynamic interactions | NSAID |
| Platelet aggregation inhibitors, including ASA, clopidogrel, prasugrel, ticagrelor | |
| Selective serotonin reuptake inhibitors (SSRI), and serotonin norepinephrine reuptake inhibitors (SNRIs) | |
| Diseases / procedures with special hemorrhagic risks | Congenital or acquired coagulation disorders |
| Thrombocytopenia or functional platelet defects | |
| Uncontrolled severe arterial hypertension | |
| Active ulcerative gastrointestinal disease | |
| Recent gastrointestinal bleeding | |
| Vascular retinopathy, such as hypertensive or diabetic | |
| Recent intracranial hemorrhage | |
| Intraspinal or intracerebral vascular abnormalities | |
| Recent brain, spinal or ophthalmological surgery | |
| Bronchiectasis or history of pulmonary bleeding | |
| Others | Age > 75 years |
Concomitant use of drugs affecting hemostasis increases the risk of bleeding. Care should be taken if patients are treated concomitantly with drugs affecting hemostasis such as non-steroidal anti-inflammatory drugs (NSAIDs), acetylsalicylic acid (ASA), platelet aggregation inhibitors or selective serotonin reuptake inhibitors (SSRI), and serotonin norepinephrine reuptake inhibitors (SNRIs) (see also 9 DRUG INTERACTIONS).
In patients with atrial fibrillation and having a condition that warrants single or dual antiplatelet therapy, a careful assessment of the potential benefits against the potential risks should be made before combining this therapy with MINT-RIVAROXABAN.
Concomitant ASA use (almost exclusively at a dose of 100 mg or less) with either rivaroxaban or warfarin during the ROCKET-AF trial was identified as an independent risk factor for major bleeding (see also 9 DRUG INTERACTIONS).
The antiplatelet agents, prasugrel and ticagrelor, have not been studied with rivaroxaban, and are not recommended as concomitant therapy.
The use of thrombolytics should generally be avoided during acute myocardial infarction (AMI) or acute stroke in patients treated with rivaroxaban, due to expected increased risk of major bleeding (see 4 DOSAGE AND ADMINISTRATION, Other situations requiring thrombolytic therapy).
Patients with malignant disease may simultaneously be at higher risk of bleeding and thrombosis than patients without malignant disease. In patients with malignant disease who undergo antithrombotic treatment with rivaroxaban, risk of bleeding may increase, in particular in the gastrointestinal, genitourinary tract or respiratory system. The individual benefit of antithrombotic treatment should be weighed against risk for bleeding in patients with active cancer dependent on tumor location, antineoplastic therapy and stage of disease.
Cardiovascular
Patients with valvular disease
MINT-RIVAROXABAN is not indicated and is not recommended for thromboprophylaxis in patients having recently undergone transcatheter aortic valve replacement (TAVR). Results from a randomized controlled clinical study (GALILEO) showed that the rivaroxaban regimen failed to demonstrate clinical benefit compared with an antiplatelet strategy. In the intention-to-treat analysis, all- cause mortality, thromboembolic and bleeding events occurred more frequently in patients randomized to the rivaroxaban regimen. A causal relationship between rivaroxaban and all-cause mortality could not be established.
Safety and efficacy of rivaroxaban have not been studied in patients with other prosthetic heart valves or other valve procedures, or those with hemodynamically significant rheumatic heart disease, especially mitral stenosis. There are no data to support that rivaroxaban provides adequate anticoagulation in patients with prosthetic heart valves, with or without atrial fibrillation. Therefore, the use of MINT-RIVAROXABAN is not recommended in this setting.
Of note, in the pivotal Phase III ROCKET AF trial that evaluated rivaroxaban in the prevention of stroke in atrial fibrillation, 14% of patients had other valvular disease including aortic stenosis, aortic regurgitation, and/or mitral regurgitation. Patients with a history of mitral valve repair were also not excluded from the study. Mitral valve repair rates are not known in ROCKET AF, since information on mitral valve repair status was not specifically collected in this study.
Patients with antiphospholipid syndrome
MINT-RIVAROXABAN is not recommended for patients with a history of thrombosis who are diagnosed with antiphospholipid syndrome. In particular for patients who are triple positive (for lupus anticoagulant, anticardiolipin antibodies, and anti-beta 2-glycoprotein I antibodies), treatment with rivaroxaban is associated with an increased rate of recurrent thrombotic events compared with vitamin K antagonists.
Patients with nonvalvular atrial fibrillation who undergo PCI (Percutaneous Coronary Intervention) with stent placement
Clinical data are available from an open label interventional study with the primary objective to assess safety in patients with nonvalvular atrial fibrillation who undergo PCI with stent placement. Data on efficacy in this population are limited (see 4 DOSAGE AND ADMINISTRATION – Patients with nonvalvular atrial fibrillation who undergo PCl with stent placement; 10.2 Pharmacodynamics, Patients with nonvalvular atrial fibrillation who undergo PCI with stent placement).
Drug Interactions
Interaction with strong inhibitors of both CYP 3A4 and P-gp
The use of MINT-RIVAROXABAN is contraindicated in patients receiving concomitant systemic treatment with strong inhibitors of both CYP 3A4 and P-gp, such as cobicistat, ketoconazole, itraconazole, posaconazole, or ritonavir. These drugs may increase rivaroxaban plasma concentrations to a clinically relevant degree, i.e, 2.6-fold on average, which increases bleeding risk.
Dronedarone should not be used concomitantly with rivaroxaban since it may increase exposure of rivaroxaban through P-gp and CYP3A4 inhibition, and thereby the risk of bleeding.
Interaction with moderate CYP 3A4 inhibitors
The azole anti-mycotic, fluconazole, a moderate CYP 3A4 inhibitor, or erythromycin, have no clinically relevant effect on rivaroxaban exposure (1.4-fold and 1.3-fold increase, respectively) and may be co-administered with MINT-RIVAROXABAN in patients with normal renal function (see 9 DRUG INTERACTIONS).
The use of rivaroxaban in subjects with mild and moderate renal impairment concomitantly treated with combined P-gp and moderate CYP 3A4 inhibitors such as erythromycin increased exposure to rivaroxaban by 1.8- and 2.0-fold, respectively, compared to subjects with normal renal function without comedication. If such use must be undertaken, caution is required.
Interaction with strong CYP 3A4 inducers
The concomitant use of rivaroxaban with strong inducers of CYP 3A4, such as rifampicin, and the anticonvulsants, phenytoin, carbamazepine, phenobarbital, reduces rivaroxaban exposure (see 9.4 Drug-Drug Interactions). Combined use of MINT-RIVAROXABAN with strong inducers should generally be avoided, since efficacy of rivaroxaban may be compromised (see 9.4 Drug-Drug Interactions).
Hepatic Impairment
Patients with significant hepatic disease (e.g, acute clinical hepatitis, chronic active hepatitis, liver cirrhosis) were excluded from clinical trials. Therefore, MINT-RIVAROXABAN is contraindicated in patients with hepatic disease (including Child-Pugh Class B and C) associated with coagulopathy and having clinically relevant bleeding risk.
The limited data available for patients with mild hepatic impairment without coagulopathy indicate that there is no difference in pharmacodynamic response or pharmacokinetics as compared to healthy subjects.
Surgery/Procedural Interventions
As with any anticoagulant, patients on rivaroxaban who undergo surgery or invasive procedures are at increased risk for bleeding. In these circumstances, temporary discontinuation of MINT-RIVAROXABAN may be required.
If a patient concomitantly receiving platelet aggregation inhibitors is to undergo elective surgery and anti-platelet effect is not desired, platelet aggregation inhibitors should be discontinued as directed by the manufacturer’s prescribing information.
Limited clinical data are available for patients undergoing fracture-related surgery of the lower limbs. These patients were from a subgroup which was not pre-specified for enrollment in an international, non-interventional (no exclusion criteria), open label cohort study designed to compare the incidence of symptomatic thromboembolic events in patients undergoing elective hip or knee surgery while not randomly assigned to treatment with rivaroxaban or any local standard-of-care pharmacological therapy.
Pre-Operative Phase
If an invasive procedure or surgical intervention is required, MINT-RIVAROXABAN 10 mg, 15 mg and 20 mg should be stopped at least 24 hours before the intervention, if possible, due to increased risk of bleeding, and based on clinical judgment of the physician. If a patient is to undergo elective surgery and anti-platelet effect is not desired, platelet aggregation inhibitors should be discontinued as per current treatment guidelines. If the procedure cannot be delayed, the increased risk of bleeding should be assessed against the urgency of the intervention. Although there are limited data, in patients at higher risk of bleeding or in major surgery where complete hemostasis may be required, consider stopping MINT-RIVAROXABAN two to four days before surgery, depending on clinical circumstances.
Peri-Operative Spinal/Epidural Anesthesia, Lumbar Puncture
When neuraxial (epidural/spinal) anesthesia or spinal puncture is performed, patients treated with antithrombotics for prevention of thromboembolic complications are at risk for developing an epidural or spinal hematoma that may result in long-term neurological injury or permanent paralysis.
The risk of these events is even further increased by the use of indwelling epidural catheters or the concomitant use of drugs affecting hemostasis. Accordingly, the use of MINT-RIVAROXABAN, at doses greater than 10 mg, is not recommended in patients undergoing anesthesia with post-operative indwelling epidural catheters. The risk may also be increased by traumatic or repeated epidural or spinal puncture. If traumatic puncture occurs, the administration of MINT-RIVAROXABAN should be delayed for 24 hours.
Patients who have undergone epidural puncture and who are receiving MINT-RIVAROXABAN 10 mg should be frequently monitored for signs and symptoms of neurological impairment (e.g, numbness or weakness of the legs, bowel or bladder dysfunction). If neurological deficits are noted, urgent diagnosis and treatment is necessary.
The physician should consider the potential benefit versus the risk before neuraxial intervention in patients anticoagulated or to be anticoagulated for thromboprophylaxis and use MINT-RIVAROXABAN 10 mg only when the benefits clearly outweigh the possible risks. An epidural catheter should not be withdrawn earlier than 18 hours after the last administration of MINT-RIVAROXABAN. MINT-RIVAROXABAN should be administered not earlier than 6 hours after the removal of the catheter in adults.
There is no clinical experience with the use of rivaroxaban 15 mg or 20 mg in these situations.
To reduce the potential risk of bleeding associated with the concurrent use of rivaroxaban and neuraxial (epidural/spinal) anesthesia or lumbar puncture, consider the pharmacokinetic profile of rivaroxaban. Placement or removal of an epidural catheter or lumbar puncture is best performed when the anticoagulant effect of rivaroxaban is estimated to be low. However, the exact timing to reach a sufficiently low anticoagulant effect in each patient is not known and should be weighed against the urgency of a diagnostic procedure.
Post-Procedural Period
MINT-RIVAROXABAN should be restarted following an invasive procedure or surgical intervention as soon as adequate hemostasis has been established and the clinical situation allows, in order to avoid unnecessary increased risk of thrombosis.
Renal Impairment
Following oral dosing with rivaroxaban, there is a direct relationship between pharmacodynamic effects and the degree of renal impairment (see 10.3 Pharmacokinetics– Renal Insufficiency).
Determine estimated creatinine clearance (eCrCl) in all patients before instituting MINT-RIVAROXABAN (see 4 DOSAGE AND ADMINISTRATION).
MINT-RIVAROXABAN should be used with caution in patients with moderate renal impairment (CrCl 30- 49 mL/min), especially in those concomitantly receiving other drugs which increase rivaroxaban plasma concentrations (see 4 DOSAGE AND ADMINISTRATION – Renal Impairment, and 9.4 Drug-Drug Interactions).
Physicians should consider the benefit/risk of anticoagulant therapy before administering MINT-RIVAROXABAN to patients with moderate renal impairment having a creatinine clearance close to the severe renal impairment category (CrCl < 30 mL/min), or in those with a potential to have deterioration of renal function to severe impairment during therapy.
In patients with severe renal impairment (CrCl 15 - < 30 mL/min), rivaroxaban plasma levels may be significantly elevated compared to healthy volunteers (1.6-fold on average) which may lead to an increased bleeding risk. Due to limited clinical data, MINT-RIVAROXABAN must be used with caution in these patients. No clinical data are available for patients with CrCl < 15 mL/min. Use is not recommended in patients with CrCl < 15mL/min. Patients who develop acute renal failure while on MINT-RIVAROXABAN should discontinue such treatment.
Due to the high plasma protein binding, i.e, about 95%, rivaroxaban is not expected to be removed by dialysis.
Anticoagulant-Related Nephropathy
There have been post-marketing reports of anticoagulant-related nephropathy (ARN) following rivaroxaban use, presenting as acute kidney injury. In patients with altered glomerular integrity or with a history of kidney disease, acute kidney injury may occur, possibly in relation to episodes of excessive anticoagulation and hematuria. A few cases have been reported in patients with no pre-existing kidney disease. Close monitoring including renal function evaluation is advised in patients with excessive anticoagulation, compromised renal function and hematuria (including microscopic).
Lactose Sensitivity
MINT-RIVAROXABAN tablets contain lactose. Patients with rare hereditary problems of lactose or galactose intolerance (e.g, the Lapp lactase deficiency or glucose-galactose malabsorption) should not take MINT-RIVAROXABAN.
Monitoring and Laboratory Tests
The prothrombin time (PT), measured in seconds, is influenced by rivaroxaban in a dose- dependent way with a close correlation to plasma concentration if the Neoplastin® reagent is used. In patients who are bleeding, measuring the PT using the Neoplastin® reagent may be useful to assist in determining an excess of anticoagulant activity (see 4 DOSAGE AND ADMINISTRATION – Considerations for INR Monitoring of VKA Activity during Concomitant MINT-RIVAROXABAN Therapy).
Although rivaroxaban therapy will lead to an elevated INR, depending on the timing of the measurement (see 10.2 Pharmacodynamics), the INR is not a valid measure to assess the anticoagulant activity of MINT-RIVAROXABAN. The INR is only calibrated and validated for VKA and should not be used for any other anticoagulant, including MINT-RIVAROXABAN.
At recommended doses, MINT-RIVAROXABAN affects the measurement of the aPTT and Heptest®. These tests are not recommended for the assessment of the pharmacodynamic effects of MINT-
RIVAROXABAN (see 10.2 Pharmacodynamics).
Converting patients from warfarin to rivaroxaban , or from rivaroxaban to warfarin, increases prothrombin time by the Neoplastin® reagent in seconds (or INR values) more than additively (e.g, individual INR values up to 12 may be observed) during concomitant therapy, whereas effects on aPTT and endogenous thrombin potential are additive (see 10.2 Pharmacodynamics).
Anti-Factor-Xa activity is influenced by rivaroxaban in a dose-dependent fashion. If it is desired to test the pharmacodynamic effects of MINT-RIVAROXABAN during the switching period, tests of anti- Factor-Xa activity can be used as they are not affected by warfarin. Use of these tests to assess the pharmacodynamic effects of MINT-RIVAROXABAN requires calibration and should not be done unless rivaroxaban-specific calibrators and controls are available (see 10.2 Pharmacodynamics).
Although there is no need for routine monitoring of anticoagulation effect of MINT-RIVAROXABAN during clinical practice, in certain infrequent situations such as overdosage, acute bleeding, urgent surgery, in cases of suspected non-compliance, or in other unusual circumstances, assessment of the anticoagulant effect of rivaroxaban may be appropriate. Accordingly, measuring PT using the Neoplastin reagent, or Factor-Xa assay using rivaroxaban-specific calibrators and controls, may be useful to inform clinical decisions in these circumstances.
7.1 Special Populations
7.1.1 Pregnant Women
No data are available on the use of rivaroxaban in pregnant women.
Based on animal data, use of rivaroxaban is contraindicated throughout pregnancy (see 2 CONTRAINDICATIONS, and 16 NON-CLINICAL TOXICOLOGY – Reproductive and Developmental Toxicology).
If MINT-RIVAROXABAN is to be used in women of childbearing potential, pregnancy should be avoided.
7.1.2 Breast-feeding
No data are available on the use of rivaroxaban in nursing mothers. In rats, rivaroxaban is secreted into breast milk. Therefore, MINT-RIVAROXABAN should only be administered after breastfeeding is discontinued (see 2 CONTRAINDICATIONS, and 16 NON-CLINICAL TOXICOLOGY – Reproductive and Development Toxicology).
7.1.3 Pediatrics
MINT-RIVAROXABAN is not indicated in children less than 18 years of age.
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Increasing age is associated with declining renal function. Both of these factors have been observed to result in increased systemic exposure to rivaroxaban, and consequently increased bleeding (see 7 WARNINGS AND PRECAUTIONS – Renal Impairment, and 4 DOSAGE AND ADMINISTRATION – Renal Impairment).
Use with caution in elderly patients, especially those taking concomitant medications that increase systemic exposure of MINT-RIVAROXABAN (see 7 WARNINGS AND PRECAUTIONS, Drug Interactions, and 9 DRUG INTERACTIONS).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
Prevention of VTE after THR or TKR
The safety of rivaroxaban 10 mg has been evaluated in three randomized, double- blind, active-control Phase III studies (RECORD 1, RECORD 2, and RECORD 3). In the Phase III studies, 4657 patients undergoing total hip replacement or total knee replacement surgery were randomized to rivaroxaban, with 4571 patients actually receiving rivaroxaban.
In RECORD 1 and 2, a total of 2209 and 1228 THR patients, respectively, were randomized to rivaroxaban 10 mg od. In RECORD 1, the treatment period for both groups was 35±4 days postoperatively. In RECORD 2, patients randomized to rivaroxaban were treated for 35 ±4 days postoperatively, and patients randomized to enoxaparin received placebo after day 12±2 until day 35±4 postoperatively. In RECORD 3, a total of 1220 TKR patients were randomized to rivaroxaban 10 mg od, and both groups received study drug until day 12±2 postoperatively.
Treatment of VTE and Prevention of Recurrent DVT and PE
The safety of rivaroxaban has been evaluated in four Phase III trials with 6790 patients treated up to 21 months. Patients were exposed to 15 mg rivaroxaban twice daily for 3 weeks followed by:
- 20 mg once daily (EINSTEIN DVT, EINSTEIN PE) or
- 20 mg once daily after at least 6 months of treatment for DVT or PE (EINSTEIN Extension), or
- 20 mg or 10 mg rivaroxaban once daily after at least 6 months of treatment for DVT or PE (EINSTEIN CHOICE).
The mean treatment duration was 194 days in EINSTEIN DVT, 183 days in EINSTEIN PE, 188 days in EINSTEIN Extension and 290 days in EINSTEIN CHOICE.
The incidence of adverse events resulting in permanent discontinuation of study drug was 5.0% for rivaroxaban and 4.4% for enoxaparin/VKA (pooled data from EINSTEIN DVT and EINSTEIN PE), 6.5% for rivaroxaban and 3.4% for placebo (EINSTEIN Extension) and 4.5% for rivaroxaban 10 mg, 4.5% for rivaroxaban 20 mg and 4.2% for ASA (EINSTEIN CHOICE).
Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation (SPAF)
In the pivotal double-blind ROCKET AF study, a total of 14,264 patients with atrial fibrillation at risk for stroke and systemic embolism were randomly assigned to treatment with either rivaroxaban (7,131) or warfarin (7,133) in 45 countries. Patients received rivaroxaban 20 mg orally once daily (15 mg orally once daily in patients with moderate renal impairment [CrCl: 30-49 mL/min]) or dose-adjusted warfarin titrated to a target INR of 2.0 to 3.0. The safety population included patients who were randomized and took at least 1 dose of study medication. In total, 14,236 patients were included in the safety population, with 7,111 and 7,125 patients in rivaroxaban and warfarin groups, respectively. The median time on treatment was 19 months and overall treatment duration was up to 41 months.
The incidence of adverse events resulting in permanent discontinuation of study drug was 15.8% in the rivaroxaban group and 15.2% in the warfarin group.
Bleeding
Due to the pharmacological mode of action, rivaroxaban is associated with an increased risk of occult or overt bleeding from any tissue and organ (see 7 WARNINGS AND PRECAUTIONS – Bleeding, and Drug Interactions). The risk of bleeding may be increased in certain patient groups, e.g, patients with uncontrolled severe arterial hypertension and/or on concomitant medication affecting hemostasis (see Table 3). The signs, symptoms, and severity (including fatal outcome) will vary according to the location and degree or extent of the bleeding and/or anemia. Hemorrhagic complications may present as weakness, paleness, dizziness, headache or unexplained swelling, dyspnea, and unexplained shock. In some cases, as a consequence of anemia, symptoms of cardiac ischemia like chest pain or angina pectoris have been observed. Known complications secondary to severe bleeding such as compartment syndrome and renal failure due to hypoperfusion have been reported for rivaroxaban. Therefore, the possibility of a hemorrhage should be considered in evaluating the medical condition in any anticoagulated patient.
Major or severe bleeding may occur and, regardless of location, may lead to disabling, life- threatening or even fatal outcomes.
Since the adverse event profiles of the patient populations treated with rivaroxaban for different indications are not interchangeable, a summary description of major and total bleeding is provided by indication, in Table 4 for VTE prevention in patients undergoing elective THR or TKR surgery, in Table 5 for Treatment of VTE and prevention of recurrent DVT and PE, in Table 6 for stroke prevention in atrial fibrillation.
Table 4 - RECORD 1, 2, and 3 (VTE Prevention After THR or TKR) – Treatment-Emergent Bleeding Events (Safety Population with Central Adjudication) in Patients Randomized to Rivaroxaban (First Dose 6 to 8 Hours Postoperatively) or Enoxaparin (First Dose 12 Hours Preoperatively)
Major Bleedinga n (%) | Major Bleeding Including Surgical Site Bleeding Events Associated With Hemoglobin Drops or Transfusions n (%) | Any Bleeding (Major or Nonmajor) n (%) | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| RECORD 1 (THR) | Rivaroxaban (N=2209) 10 mg od po for 35±4 days | 6 (0.3) | 40 (1.8) | 133 (6.0) | ||||||
Enoxaparin (N=2224) 40 mg od SC for 36±4 days | 2 (0.1) | 33 (1.5) | 131 (5.9) | |||||||
| P-Value | 0.18 | 0.41 | 0.90 | |||||||
| RECORD 2 (THR) | Rivaroxaban (N=1228) 10 mg od po for 35±4 days | 1 (0.1) | 23 (1.9) | 81 (6.6) | ||||||
Enoxaparin (N=1229) 40 mg od SC for 12±2 days | 1 (0.1) | 19 (1.6) | 68 (5.5) | |||||||
| P-Value | 1.00 | 0.54 | 0.273 | |||||||
| RECORD 3 (TKR) | Rivaroxaban (N=1220) 10 mg od po for 12±2 days | 7 (0.6) | 21 (1.7) | 60 (4.9) | ||||||
Enoxaparin (N=1239) 40 mg od SC for 13±2 days | 6 (0.5) | 17 (1.4) | 60 (4.8) | |||||||
| P-Value | 0.79 | 0.52 | 1.00 | |||||||
| Pooled Analysis (RECORD 1, 2, 3) | Rivaroxaban (N=4657) | 14 (0.3) | 84 (1.8) | 274 (5.9) | ||||||
| Enoxaparin (N=4692) 40 mg od SC | 9 (0.2) | 69 (1.5) | 259 (5.5) | |||||||
| P-Value | 0.31 | 0.22 | 0.48 | |||||||
a Major bleeding events included: (1) fatal, (2) bleeding into a critical organ (e.g, retroperitoneal, intracranial, intraocular or intraspinal bleeding/hemorrhagic puncture), (3) bleeding requiring reoperation, (4) clinically overt extra-surgical site bleeding associated with ≥2 g/dL fall in hemoglobin or leading to infusion of ≥2 units of whole blood or packed cells.
See Table 19 and Table 21 for additional details.
od = once daily, po = oral, SC = subcutaneous
Table 5 - Treatment-Emergent Bleeding Events and Results – Safety Population with Central Adjudication - Pooled Analysis, EINSTEIN DVT, EINSTEIN PE, EINSTEIN Extension and EINSTEIN CHOICE (Treatment of VTE and Prevention of Recurrent DVT and PE)
| Pooled EINSTEIN DVT and EINSTEIN PE | EINSTEIN Extension | EINSTEIN CHOICE | |||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Bleeding event | Rivaroxaban N=4130 | Enox/VKA N=4116 | HR (95%CI) P-value for superiority | 20 mg od N=598 | Placebo N=590 | Rivaroxaban 10 mg N=1127 | Rivaroxaban 20 mg N=1107 | ASA 100 mg N=1131 | |||||||||||||||||||
| n (%) | n (%) | n (%) | n (%) | n (%) | n (%) | n (%) | |||||||||||||||||||||
| Major and Clinically Relevant Non-major Bleedinga | 388 (9.4) | 412 (10.0) | 0.93 (0.81-1.06) P=0.27 | 36 (6.0) | 7 (1.2) | 27 (2.4) | 36 (3.3) | 23(2.0) | |||||||||||||||||||
| Major bleedingb | 40 (1.0) | 72 (1.7) | 0.54 (0.37-0.80) P=0.0018* | 4 (0.7)b | 0 | 5 (0.4) | 6 (0.5) | 3 (0.3) | |||||||||||||||||||
| Fatal Bleeding | 3 (<0.1) | 8 (0.2) | - | 0 | 0 | 0 | 1 (<0.1) | 1 (<0.1) | |||||||||||||||||||
| Intracranial | 2 (<0.1) | 4 (<0.1) | - | 0 | 0 | 0 | 0 | 1 (<0.1) | |||||||||||||||||||
Non-Fatal Critical Organ Bleeding | 10 (0.2) | 29 (0.7) | - | 0 | 0 | 2 (0.2) | 4 (0.4) | 1 (<0.1) | |||||||||||||||||||
| Intracranial | 3 (<0.1) | 10 (0.2) | - | 0 | 0 | 1 (<0.1) | 3 (0.3) | 1 (<0.1) | |||||||||||||||||||
Non-Fatal Non-Critical Organ Bleeding (Fall in Hb ≥ 2 g/dL and/or Transfusions ≥ 2 Units | 27 (0.7) | 37 (0.9) | - | 4 | 0 | 3 (0.3) | 1 (<0.1) | 1 (<0.1) | |||||||||||||||||||
| Gastrointestinal | 12 (0.3) | 20 (0.5) | - | 3 | 0 | 2 (0.2) | 1 (<0.1) | 1 (<0.1) | |||||||||||||||||||
| Clinically Relevant Non-Major Bleeding | 357 (8.6) | 357 (8.7) | 0.99 (0.85-1.14) P=0.84 | 32 (5.4)b | 7 (1.2) | 22 (2.0) | 30 (2.7) | 20 (1.8) | |||||||||||||||||||
- a Primary safety outcome for Pooled EINSTEIN DVT and EINSTEIN PE.
- b Primary safety outcome for EINSTEIN Extension and EINSTEIN CHOICE. Major bleeding event was defined as overt bleeding associated with a fall in hemoglobin of 2 g/dL or more; or leading to a transfusion of 2 or more units of packed red blood cells or whole blood; or that occurred in a critical site: intracranial, intraocular, pericardial, intra-articular, intramuscular with compartment syndrome, retroperitoneal; or contributing to death. In EINSTEIN Extension, some patients had more than one event.
* statistically significant at nominal 0.05
See Table for definition of other footnotes.
Clinically relevant non-major bleeding pooled from both EINSTEIN DVT and EINSTEIN PE from a mucosal site occurred in 7.2 % of patients in the rivaroxaban group and 6.0 % of subjects in the enoxaparin/VKA group. Major bleeding from a mucosal site was observed in 0.6 % of the rivaroxaban group and 0.7 % of the enoxaparin/VKA group.
Table 6 - ROCKET AF (Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation (SPAF))–Time to the First Occurrence of Bleeding Events While on Treatment (up to Last Dose Plus 2 Days) - Safety Analysis
| Rivaroxaban | Warfarin | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| n (%/year) | n (%/year) | HR (95% CI); P-value | ||||||||
| Major and Non-major Clinically Relevant Bleeding | 1475 | (14.91) | 1449 | (14.52) | 1.03 (0.96,1.11); 0.442 | |||||
| Major Bleedinga | 395 | (3.60) | 386 | (3.45) | 1.04 (0.90,1.20); 0.576 | |||||
| Hemoglobin Drop | 305 | (2.77) | 254 | (2.26) | 1.22 (1.03,1.44); 0.019* | |||||
| Transfusion (> 2 units) | 183 | (1.65) | 149 | (1.32) | 1.25 (1.01,1.55); 0.044* | |||||
| Critical Organ Bleed | 91 | (0.82) | 133 | (1.18) | 0.69 (0.53,0.91); 0.007* | |||||
| Intracranial Hemorrhage | 55 | (0.49) | 84 | (0.74) | 0.67 (0.47, 0.94); 0.019* | |||||
| Fatal Bleed | 27 | (0.24) | 55 | (0.48) | 0.50 (0.31,0.79); 0.003* | |||||
| Non-major Clinically Relevant Bleeding | 1185 | (11.80) | 1151 | (11.37) | 1.04 (0.96,1.13); 0.345 | |||||
a See Table and Table 5 for definition of other footnotes.
- Statistically significant at nominal 0.05 (two-sided).
See Table 28, Table 32, and Table 34 for additional details.
Mucosal major bleeding was more common in the rivaroxaban group (2.4%/year) as compared to the warfarin group (1.6%/year; HR 1.52 (1.25, 1.83) P < 0.001). Most of the mucosal major bleeding was from a gastrointestinal site.
Intracranial hemorrhage and upper gastrointestinal hemorrhage resulting in death were observed in 24/55 (43.6%) and 1/204 (0.5%) rivaroxaban patients who experienced these adverse events, respectively, compared to 42/84 (50.0%) and 3/125 (2.4%) warfarin patients who experienced these same events, respectively.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
The most common treatment-emergent adverse events in the three Phase III studies for VTE prevention in elective THR and TKR surgery are presented below in Table 7.
Table 7 Treatment-Emergent Adverse Drug Reactions Occurring in >1% of Any Treatment Group – Pooled Data of RECORD 1, 2, 3 (VTE Prevention After THR or TKR) – (Patients Valid for Safety Analysisa)
| Rivaroxaban (N=4571) | Enoxaparin (N=4601) | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| n | (%) | n | (%) | |||||||
| Blood and lymphatic system disorders | ||||||||||
| Thrombocytosis (including platelet count increased) | 77 | (1.68) | 86 | (1.87) | ||||||
| Gastrointestinal disorders | ||||||||||
| Nausea | 402 | (8.79) | 402 | (8.74) | ||||||
| Diarrhea | 101 | (2.21) | 134 | (2.91) | ||||||
| Abdominal and gastrointestinal pain (including upper abdominal pain, stomach discomfort) | 88 | (1.93) | 88 | (1.91) | ||||||
| Dyspepsia (including epigastric discomfort) | 40 | (0.88) | 49 | (1.06) | ||||||
| Vomiting | 371 | (8.12) | 392 | (8.52) | ||||||
| Constipation | 293 | (6.41) | 319 | (6.93) | ||||||
| General Disorders and Administration Site Conditions | ||||||||||
| Fever | 420 | (9.19) | 427 | (9.28) | ||||||
| Decreased general strength and energy (including asthenia, fatigue) | 56 | (1.23) | 45 | (0.98) | ||||||
| Edema peripheral | 190 | (4.16) | 160 | (3.48) | ||||||
| Injury, poisoning, and post-procedural complications | ||||||||||
| Anemia (including laboratory parameter) | 263 | (5.75) | 292 | (6.35) | ||||||
| Post procedural hemorrhage | 200 | (4.38) | 192 | (4.17) | ||||||
| Wound secretion | 125 | (2.73) | 92 | (2.00) | ||||||
| Investigations | ||||||||||
| Increase in LDH | 37 | (0.81) | 49 | (1.06) | ||||||
| Increase in transaminases | 123 | (2.69) | 190 | (4.13) | ||||||
| Increase in Gamma-glutamyltransferase | 74 | (1.62) | 121 | (2.63) | ||||||
| Increase in alkaline phosphatase | 35 | (0.77) | 56 | (1.22) | ||||||
| Musculoskeletal, Connective Tissue, and Bone Disorders | ||||||||||
| Pain in extremity | 74 | (1.62) | 55 | (1.20) | ||||||
| Nervous System Disorders | ||||||||||
| Dizziness | 149 | (3.26) | 142 | (3.09) | ||||||
| Headache | 105 | (2.30) | 96 | (2.09) | ||||||
| Syncope (including loss of consciousness) | 71 | (1.55) | 37 | (0.80) | ||||||
| Skin and subcutaneous tissue disorders | ||||||||||
| Pruritus (including uncommon cases of generalized pruritus) | 97 | (2.12) | 73 | (1.59) | ||||||
| Rash | 56 | (1.23) | 57 | (1.24) | ||||||
| Vascular disorders | ||||||||||
| Hypotension (including blood pressure decreased) | 146 | (3.19) | 147 | (3.19) | ||||||
| Hematoma | 47 | (1.03) | 53 | (1.15) | ||||||
Note: Incidence = number of events/number at risk, where: number of events = number of patients reporting the event; number at risk = number of patients in reference population
Only treatment emergent adverse events which occurred up to 2 days after the last dose of study medication are included.
- a. Started after administration of oral study medication (rivaroxaban or matching placebo tablet).
The most common treatment-emergent adverse events reported by patients valid for safety analysis in the 3 Phase III studies for treatment of VTE and prevention of recurrent DVT and PE are presented in Table 8.
Table 8 - Treatment-Emergent Adverse Reactions occurring in >1% of Any Treatment Group – pooled EINSTEIN DVT (11702 DVT) and EINSTEIN PE (11702 PE); EINSTEIN Extension (11899); EINSTEIN CHOICE (16416) b (Treatment of VTE and Prevention of Recurrent DVT and PE) – Safety Analysis
Pooled EINSTEIN DVT and EINSTEIN PE | EINSTEIN Extension | EINSTEIN CHOICE | ||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Rivaroxaban (N=4130) n (%) | ENOXAPARIN/ VKA (N=4116) n (%) | Rivaroxaban (N=598) n (%) | Placebo (N=590) n (%) | Rivaroxaban 10 mg (N=1127) n (%) | Rivaroxaban 20 mg (N=1107) n (%) | ASA 100 mg (N= 1131) n (%) | ||||||||||||||
| Blood and lymphatic system disorders | 84 (2.03) | 62 (1.51) | 4 (0.67) | 2 (0.34) | 1 (<0.1) | 3 (0.3) | 0 | |||||||||||||
| Anemia | ||||||||||||||||||||
| Cardiac disorder | 55 (1.33) | 43 (1.04) | 2 (0.33) | 0 | 0 | 1 (<0.1) | 0 | |||||||||||||
| Tachycardia | ||||||||||||||||||||
| Eye disorders | 39 (0.94) | 47 (1.14) | 6 (1.00) | 0 | 2 (0.2) | 6 (0.5) | 4 (0.4) | |||||||||||||
Conjunctival hemorrhage | ||||||||||||||||||||
| Gastrointestinal disorders | ||||||||||||||||||||
Gingival bleeding | 93 (2.25) | 104 (2.53) | 11 (1.84) | 2 (0.34) | 14 (1.2) | 28 (2.5) | 12 (1.1) | |||||||||||||
Rectal hemorrhage | 90 (2.18) | 56 (1.36) | 4 (0.67) | 4 (0.68) | 9 (0.8) | 6 (0.2) | 7 (0.6) | |||||||||||||
| Abdominal pain | 69 (1.67) | 53 (1.29) | 2 (0.33) | 7 (1.19) | 1 (<0.1) | 3 (0.3) | 2 (0.2) | |||||||||||||
Abdominal pain upper | 71 (1.72) | 50 (1.21) | 10 (1.67) | 1 (0.17) | 2 (0.2) | 2 (0.2) | 5 (0.4) | |||||||||||||
| Constipation | 187 (4.53) | 174 (4.23) | 6 (1.00) | 5 (0.85) | 2 (0.2) | 0 | 7 (0.6) | |||||||||||||
| Diarrhea | 179 (4.33) | 164 (3.98) | 7 (1.17) | 8 (1.36) | 4 (0.4) | 4 (0.4) | 1 (<0.1) | |||||||||||||
| Dyspepsia | 60 (1.45) | 54 (1.31) | 8 (1.34) | 4 (0.68) | 1 (<0.1) | 3 (0.3) | 4 (0.4) | |||||||||||||
| Nausea | 153 (3.70) | 160 (3.89) | 7 (1.17) | 6 (1.02) | 3 (0.3) | 3 (0.3) | 2 (0.2) | |||||||||||||
| Vomiting | 69 (1.67) | 96 (2.33) | 3 (0.50) | 6 (1.02) | 0 | 4 (0.4) | 2 (0.2) | |||||||||||||
| General disorders and administration site conditions | ||||||||||||||||||||
| Pyrexia | 111 (2.69) | 108 (2.62) | 5 (0.84) | 7 (1.19) | 1 (<0.1) | 2 (0.2) | 0 | |||||||||||||
| Edema peripheral | 128 (3.10) | 135 (3.28) | 13 (2.17) | 17 (2.88) | 0 | 0 | 1 (<0.1) | |||||||||||||
| Asthenia | 61 (1.48) | 60 (1.46) | 4 (0.67) | 6 (1.02) | 1 (<0.1) | 1 (<0.1) | 1 (<0.1) | |||||||||||||
| Fatigue | 90 (2.18) | 68 (1.65%) | 6 (1.00) | 3 (0.51) | 1 (<0.1) | 1 (<0.1) | 3 (0.3) | |||||||||||||
| Injury, poisoning and post-procedural complications | ||||||||||||||||||||
Pooled EINSTEIN DVT and EINSTEIN PE | EINSTEIN Extension | EINSTEIN CHOICE | ||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Rivaroxaban (N=4130) n (%) | ENOXAPARIN/ VKA (N=4116) n (%) | Rivaroxaban (N=598) n (%) | Placebo (N=590) n (%) | Rivaroxaban 10 mg (N=1127) n (%) | Rivaroxaban 20 mg (N=1107) n (%) | ASA 100 mg (N= 1131) n (%) | ||||||||||||||||
| Wound hemorrhage | 59 (1.43) | 65 (1.58) | 11 (1.84) | 7 (1.19 ) | 11 (1.0) | 11(1.0) | 8 (0.7) | |||||||||||||||
| Contusion | 145 (3.51) | 197 (4.79) | 19 (3.18) | 16 (2.71) | 0 | 2 (0.2) | 0 | |||||||||||||||
| Subcutaneous hematoma | 44 (1.07) | 61 (1.48) | 0 | 2 (0.34) | 33 (2.9) | 24 (2.2) | 33 (2.9) | |||||||||||||||
| Investigations | ||||||||||||||||||||||
| Alanine aminotransferase increasedc | 72 (1.74 ) | 129 (3.13 ) | 2 (0.33) | 4 (0.68) | - | - | - | |||||||||||||||
| Aspartate aminotransferase increasedc | 32 (0.77) | 44 (1.07) | 4 (0.67) | 3 (0.51) | - | - | - | |||||||||||||||
| Musculoskeletal, connective tissue and bone disorders | 230 (5.57) | 221 (5.37) | 29 (4.85) | 35 (5.93) | 4 (0.4) | 2 (0.2) | 1 (<0.1) | |||||||||||||||
| Pain in extremity | ||||||||||||||||||||||
| Nervous system disorders | ||||||||||||||||||||||
| Headache | 284 (6.88) | 242 (5.88) | 18 (3.01) | 15 (2.54) | 3 (0.3) | 4 (0.4) | 3 (0.3) | |||||||||||||||
| Dizziness | 102 (2.47) | 108 (2.62) | 6 (1.00) | 8 (1.36 ) | 5 (0.4) | 4 (0.4) | 3 (0.3) | |||||||||||||||
| Renal and urinary disorders | 111 (2.69) | 113 (2.75) | 13 (2.17) | 2 (0.34) | 0 | 3 (0.3) | 0 | |||||||||||||||
| Hematuria | ||||||||||||||||||||||
| Reproductive system and breast disorders | ||||||||||||||||||||||
| Menorrhagiaa | 122 (2.95) | 64 (1.55) | 5 (0.84) | 2 (0.34) | 10 (0.9) | 15 (1.4) | 2 (0.2) | |||||||||||||||
| Vaginal hemorrhage | 54 (1.31) | 23 (0.56) | 1 (0.17) | 5 (0.85) | 4 (0.4) | 5 (0.5) | 2 (0.2) | |||||||||||||||
Respiratory, thoracic and mediastinal disorders | ||||||||||||||||||||||
| Epistaxis | 307 (7.43) | 271 (6.58) | 24 (4.01) | 11 (1.86) | 41 (3.6) | 41 (3.7) | 29 (2.6) | |||||||||||||||
| Hemoptysis | 100 (2.42) | 98 (2.38) | 1 (0.17) | 1 (0.17) | 0 | 6 (0.5) | 1 (<0.1) | |||||||||||||||
Skin and subcutaneous tissue disorders | ||||||||||||||||||||||
| Pruritus | 83 (2.01 ) | 58 (1.41) | 2 (0.33 ) | 2 (0.34) | 8 (0.7) | 3 (0.3) | 3 (0.3) | |||||||||||||||
| Rash | 97 (2.35) | 89 (2.16 ) | 5 (0.84) | 7 (1.19) | 5 (.4) | 3 (0.3) | 4 (0.4) | |||||||||||||||
Vascular disorders Hematoma | 91 (2.20) | 150 (3.64) | 7 (1.17) | 8 (1.36) | 0 | 1 (<0.1) | 1 (<0.1) | |||||||||||||||
NB: - Percentages calculated with the number of subjects in each group as denominator
- Incidence is based on number of subjects, not number of events
- Treatment-Emergent (pooled EINSTEIN DVT and EINSTEIN PE) = events that start after randomization and up to 2 days after the last dose of study medication
- Treatment-Emergent (EINSTEIN Extension) = events that start on or after the first dose of study medication and up to 2 days after the last dose of study medication
a Observed as very common for rivaroxaban in women <55 years in pooled 11702 DVT and 11702 PE studies b According to the protocol, a targeted AE reporting was applied in this study, i.e. all serious adverse events
(SAEs), all AEs of special interest, independent if serious or not, all non-serious AEs leading to a permanent study medication discontinuation, and all pregnancies (and their outcomes) in a patient or of the patient’s partner needed to be captured on the eCRF and were reported to PV within 24 hours. Investigators could collect AEs on the eCRF, if deemed important.
c As laboratory measurements related to AST/ALT in Einstein CHOICE were not scheduled but performed as needed, the information is not available
The most common identified treatment-emergent adverse drug reactions in the pivotal Phase III study, ROCKET AF, for prevention of stroke and systemic embolism in patients with atrial fibrillation are presented in Table 9.
Table 9 - Treatment-Emergent Adverse Reactions Occurring in >1% of Any Treatment Group – ROCKET AF (Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation (SPAF)) - Safety Analysis
Rivaroxaban (N=7111) | Warfarin (N=7125) | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| n | (%) | n | (%) | ||||||
| Blood and lymphatic system disorders | |||||||||
| Anemia | 219 | (3.08) | 143 | (2.01) | |||||
| Eye disorders | |||||||||
| Conjunctival hemorrhage | 104 | (1.46) | 151 | (2.12) | |||||
| Gastrointestinal disorders | |||||||||
Diarrhea Gingival bleeding Nausea Rectal hemorrhage Abdominal pain upper Vomiting Dyspepsia Abdominal pain Gastrointestinal hemorrhage | 379 263 194 149 127 114 111 107 100 | (5.33) (3.70) (2.73) (2.10) (1.79) (1.60) (1.56) (1.50) (1.41) | 397 155 153 102 120 111 91 118 70 | (5.57) (2.18) (2.15) (1.43) (1.68) (1.56) (1.28) (1.66) (0.98) | |||||
| General Disorders and Administration Site Conditions | |||||||||
| Edema peripheral | 435 | (6.12) | 444 | (6.23) | |||||
| Fatigue | 223 | (3.14) | 221 | (3.10) | |||||
| Asthenia | 125 | (1.76) | 106 | (1.49) | |||||
| Pyrexia | 72 | (1.01) | 87 | (1.22) | |||||
| Injury, poisoning and post-procedural complications | |||||||||
| Contusion | 196 | (2.76) | 291 | (4.08) | |||||
| Investigations | |||||||||
| Alanine aminotransferase increased | 144 | (2.03) | 112 | (1.57) | |||||
| Musculoskeletal, Connective Tissue, and Bone Disorders | |||||||||
| Pain in extremity | 191 | (2.69) | 208 | (2.92) | |||||
| Nervous System Disorders | |||||||||
| Dizziness | 433 | (6.09) | 449 | (6.30) | |||||
Rivaroxaban (N=7111) | Warfarin (N=7125) | ||||||||
|---|---|---|---|---|---|---|---|---|---|
| n | (%) | n | (%) | ||||||
| Headache | 324 | (4.56) | 363 | (5.09) | |||||
| Syncope | 130 | (1.83) | 108 | (1.52) | |||||
| Renal and urinary disorders | |||||||||
| Hematuria | 296 | (4.16) | 242 | (3.40) | |||||
| Respiratory tract disorders | |||||||||
| Epistaxis | 721 | (10.14) | 609 | (8.55) | |||||
| Hemoptysis | 99 | (1.39) | 100 | (1.40) | |||||
| Skin and subcutaneous tissue disorders | |||||||||
| Ecchymosis | 159 | (2.24) | 234 | (3.28) | |||||
| Pruritus | 120 | (1.69) | 118 | (1.66) | |||||
| Rash | 112 | (1.58) | 129 | (1.81) | |||||
| Vascular disorders | |||||||||
| Hematoma | 216 | (3.04) | 330 | (4.63) | |||||
| Hypotension | 141 | (1.98) | 130 | (1.82) | |||||
NB: Incidence is based on number of subjects, not number of events
Treatment-Emergent = events that start on or after the first dose of study medication and up to 2 days after the last dose of study medication
8.3 Less Common Clinical Trial Adverse Reactions
Incidence is ≥0.1% to <1% unless specified.
VTE Prevention in Elective THR and TKR Surgery
Cardiac Disorders: tachycardia
Gastrointestinal Disorders: dry mouth, gastrointestinal tract hemorrhage (including gingival bleeding, rectal hemorrhage, hematemesis)
General Disorders and Administration Site Conditions: feeling unwell (including malaise), localized edema
Hepatobiliary Disorders: hepatic impairment (≥0.01% to <0.1%)
Immune System Disorders: hypersensitivity, anaphylaxis, allergic edema and angioedema, dermatitis allergic
Investigations: bilirubin conjugated increased (with or without concomitant increase of ALT) (≥ 0.01% to < 0.1%), blood bilirubin increased, increased amylase, increased lipase
Renal and Urinary Disorders: renal impairment (including serum creatinine increased, blood urea increased)
Respiratory Tract Disorders: epistaxis
Skin and Subcutaneous Tissue Disorders: contusion, urticaria (including rare cases of generalized urticaria)
Vascular Disorders: urogenital tract hemorrhage
Treatment of VTE and Prevention of Recurrent DVT and PE
Incidence is ≥ 0.1% to < 1% (pooled EINSTEIN DVT, EINSTEIN PE and EINSTEIN Extension) unless specified. Patients rolled over from EINSTEIN DVT or EINSTEIN PE into EINSTEIN Extension are considered as one patient (N=4556).
Cardiac Disorder: tachycardia
Gastrointestinal Disorders: gastrointestinal hemorrhage, hematochezia, hemorrhoidal hemorrhage, melena, mouth hemorrhage, abdominal discomfort, abdominal pain lower, dry mouth
General Disorders and Administration Site Conditions: asthenia, feeling abnormal, malaise
Hepatobiliary Disorders: hepatic impairment
Immune System Disorders: hypersensitivity
Injury, Poisoning and Post-procedural Complications: post-procedural hemorrhage, traumatic hematoma, traumatic hemorrhage, subcutaneous hematoma
Investigations: hemoglobin decreased, aspartate aminotransferase increased, liver function test abnormal, hepatic enzyme increased, transaminases increased, blood bilirubin increased, bilirubin conjugated increased (with or without concomitant increase of ALT), gamma-glutamyl transferase increased, blood alkaline phosphatase increased
Nervous System Disorders: syncope, cerebral and intra cranial hemorrhage (≥ 0.01% to < 0.1%)
Reproductive System and Breast disorders: menometrorrhagia, metrorrhagia
Skin and Subcutaneous Tissue Disorders: urticaria, ecchymosis, skin hemorrhage, dermatitis allergic (≥0.01% to <0.1%)
Vascular Disorders: hypotension
In other clinical studies with rivaroxaban, occurrences of vascular pseudoaneurysm formation following percutaneous intervention have been observed. Very rare cases of adrenal hemorrhage have been reported.
Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation (SPAF)
Cardiac disorders: tachycardia
Eye disorders: eye hemorrhage, vitreous hemorrhage
Gastrointestinal Disorders: melena, upper gastrointestinal hemorrhage, hemorrhoidal hemorrhage, hematochezia, mouth hemorrhage, lower gastrointestinal hemorrhage, anal hemorrhage, gastric ulcer hemorrhage, gastritis hemorrhagic, gastric hemorrhage, hematemesis, abdominal discomfort, abdominal pain lower, dry mouth
General Disorders and Administration Site Conditions: malaise
Hepatobiliary Disorders: hepatic impairment, hyperbilirubinemia, jaundice (≥ 0.01% to < 0.1%)
Immune System Disorders: hypersensitivity, anaphylaxis (≥ 0.01% to < 0.1%), allergic edema and angioedema
Injury, Poisoning, and Post-procedural Complications: post-procedural hemorrhage, wound hemorrhage, traumatic hematoma, incision site hemorrhage, subdural hematoma, subcutaneous hematoma, periorbital hematoma
Investigations: hemoglobin decreased, hematocrit decreased, blood bilirubin increased, liver function test abnormal, aspartate aminotransferase increased, hepatic enzyme increased, blood urine present, creatinine renal clearance decreased, blood creatinine increased, blood urea increased, blood alkaline phosphatase increased, lipase increased, bilirubin conjugated increased (with or without concomitant increase of ALT) (≥ 0.01% to < 0.1%)
Musculoskeletal, Connective Tissue, and Bone Disorders: hemarthrosis, muscle hemorrhage (≥ 0.01% to < 0.1%)
Nervous system disorders: loss of consciousness, hemorrhagic stroke, hemorrhage intracranial
Renal and urinary disorders: renal impairment
Reproductive system disorders: vaginal hemorrhage, metrorrhagia
Skin and Subcutaneous Tissue Disorders: dermatitis allergic, rash pruritic, rash erythemateous, rash generalized, pruritus generalized, urticaria, skin hemorrhage
Vascular disorders: hemorrhage, bleeding varicose vein
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and Other Quantitative Data
Clinical Trial Findings
In Phase III clinical trials, in VTE prevention, Treatment of VTE and prevention of recurrent DVT and PE, and SPAF the incidence of increases in transaminases in the rivaroxaban and comparator arms were similar, see Table 7, Table 8, and Table 9 above.
8.5 Post-Market Adverse Reactions
The following adverse reactions have been identified during post-approval use of rivaroxaban. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
- : agranulocytosis, thrombocytopenia
- cholestasis, hepatitis (including hepatocellular injury)
- anaphylaxis, allergic edema and angioedema (with or without urticaria)
- Anticoagulant-related nephropathy
- eosinophilic pneumonia
Skin and Subcutaneous Tissue Disorders: Stevens-Johnson syndrome, drug reaction with eosinophilia and systemic symptoms (DRESS)
9 DRUG INTERACTIONS
9.2 Drug Interactions Overview
Rivaroxaban neither inhibits nor induces CYP 3A4 or any other major CYP isoenzymes.
Concomitant use of drugs affecting hemostasis increases the risk of bleeding. Care should be taken if patients are treated concomitantly with drugs affecting hemostasis such as nonsteroidal anti-inflammatory drugs (NSAIDs), acetylsalicylic acid, and platelet aggregation inhibitors. Due to the increased bleeding risk, generally avoid concomitant use with other anticoagulants (see 7 WARNINGS AND PRECAUTIONS – Bleeding).
9.4 Drug-Drug Interactions
The use of MINT-RIVAROXABAN is contraindicated in patients receiving concomitant systemic treatment with strong inhibitors of both CYP 3A4 and P-gp such as cobicistat, ketoconazole, itraconazole, posaconazole, or ritonavir). These drugs may increase rivaroxaban plasma concentrations to a clinically relevant degree, i.e., 2.6-fold on average, which may lead to bleeding. The azole anti- mycotic, fluconazole, a moderate CYP 3A4 inhibitor, has less effect on rivaroxaban exposure and may be co-administered with caution (see 2 CONTRAINDICATIONS, and 7 WARNINGS AND PRECAUTIONS – Drug Interactions).
In the ROCKET AF clinical trial in patients with atrial fibrillation, no apparent increase in major bleeding was observed in patients in whom amiodarone, a moderate CYP 3A4 inhibitor, was co- administered with rivaroxaban.
Drugs strongly inhibiting only one of the rivaroxaban elimination pathways, either CYP 3A4 or P-gp, are expected to increase rivaroxaban plasma concentrations to a lesser extent. The expected increase is considered less clinically relevant, see Table 10.
Table 10 - Established or Potential Drug-Drug Interactions
| Concomitant Drug Class: Drug Name | Reference | Effect | Clinical comment |
Azole antimycotic: ketoconazole | CT | Co-administration of rivaroxaban with the azole-antimycotic ketoconazole (400 mg od) a strong CYP 3A4 and P-gp inhibitor, led to a 2.6-fold increase in mean rivaroxaban steady state AUC and a 1.7-fold increase in mean rivaroxaban Cmax, with significant increases in its pharmacodynamic effects. | The use of MINT-RIVAROXABAN is contraindicated in patients receiving systemic treatment with ketoconazole (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS– Drug Interactions and Renal Impairment). |
| Cobicistat | C | Cobicistat is a strong CYP 3A4 and P-gp inhibitor. Coadministration with cobicistat may result in increased plasma concentration of rivaroxaban, leading to an increased bleeding risk. | The use of MINT-RIVAROXABAN is contraindicated in patients receiving systemic treatment with cobicistat (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS – Drug Interactions). |
| Concomitant Drug Class: Drug Name | Reference | Effect | Clinical comment |
| Dronedarone | C | In a retrospective cohort study using the Truven Health MarketScan database in the US, a significantly increased risk of ICD-diagnoses of bleeding leading to hospitalization or emergency department visit was observed, driven by gastrointestinal bleeding, in NVAF patients with the concomitant use of rivaroxaban and dronedarone compared to those taking rivaroxaban alone. | Dronedarone should not be used concomitantly with MINT-RIVAROXABAN since it may increase exposure of rivaroxaban through P-gp and CYP3A4 inhibition, and thereby the risk of bleeding. |
| fluconazole | CT | Administration of the moderate CYP 3A4 inhibitor fluconazole (400 mg once daily) led to a 1.4-fold increase in mean rivaroxaban AUC and a 1.3-fold increase in mean Cmax. | No dose adjustment is required. |
Protease inhibitor: ritonavir | CT | Co-administration of rivaroxaban with the HIV protease inhibitor ritonavir (600 mg bid), a strong CYP 3A4 and P-gp inhibitor, led to a 2.5-fold increase in mean rivaroxaban AUC and a 1.6-fold increase in mean rivaroxaban Cmax, with significant increases in its pharmacodynamic effects. | The use of MINT-RIVAROXABAN is contraindicated in patients receiving systemic treatment with ritonavir (see 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS – Drug Interactions and Renal Impairment). |
Anti-infectives: erythromycin | CT | Erythromycin (500 mg tid), which inhibits CYP 3A4 and P-gp moderately, led to a 1.3-fold increase in mean rivaroxaban AUC and Cmax. | No dose adjustment is required. For patients with renal impairment See 7 WARNINGS AND PRECAUTIONS – Drug Interactions and 10.3 Pharmacokinetics–Special Populations and Conditions – Renal Insufficiency |
| Concomitant Drug Class: Drug Name | Reference | Effect | Clinical comment |
| clarithromycin | CT | Clarithromycin (500 mg bid), considered a strong CYP 3A4 inhibitor and moderate P-gp inhibitor, led to a 1.5-fold increase in mean rivaroxaban, and a 1.4-fold increase in Cmax. | The use of MINT-RIVAROXABAN in combination with clarithromycin may increase the risk of bleeding particularly in patients with underlying disease conditions, and elderly. Caution is required. |
| rifampicin | CT | Co-administration of rivaroxaban with the strong CYP 3A4 and P-gp inducer rifampicin led to an approximate 50% decrease in mean rivaroxaban AUC, with parallel decreases in its pharmacodynamic effects. | Strong CYP 3A4 inducers should generally be avoided in combination with MINT-RIVAROXABAN, as such use can be expected to result in inadequate anticoagulation. |
Anticonvulsants: phenytoin carbamazepine phenobarbital | T | The concomitant use of rivaroxaban with strong CYP 3A4 inducers (e.g, phenytoin, carbamazepine, or phenobarbital) may also lead to a decreased rivaroxaban plasma concentration. | Strong CYP 3A4 inducers should generally be avoided in combination with MINT-RIVAROXABAN, as such use can be expected to result in inadequate anticoagulation. |
Nonsteroidal Anti- inflammatory Drugs (NSAID): naproxen | CT | Co-administration with naproxen did not affect rivaroxaban bioavailability and pharmacokinetics. No clinically relevant prolongation of bleeding time was observed when 500 mg naproxen was pre-administered 24 hours before concomitant administration of single doses of rivaroxaban 15 mg and naproxen 500 mg in healthy subjects. | Concomitant use with MINT-RIVAROXABAN may increase the risk of bleeding. Promptly evaluate any signs or symptoms of blood loss (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions). |
| Concomitant Drug Class: Drug Name | Reference | Effect | Clinical comment |
| acetylsalicylic acid (ASA) | CT | No clinically significant pharmacokinetic or pharmacodynamic interactions were observed when 500 mg ASA was pre-administered 24 hours before concomitant administration of single doses of rivaroxaban 15 mg and ASA 100 mg in healthy subjects. | Concomitant use with MINT-RIVAROXABAN increases the risk of bleeding. Promptly evaluate any signs or symptoms of blood loss (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions). For patients in the ROCKET AF trial, concomitant ASA use (almost exclusively at 100 mg or less) was identified as an independent risk factor for major bleeding with both rivaroxaban and warfarin. |
Antiplatelet drugs: clopidogrel | CT | In two drug interaction studies of 11 and 13 healthy subjects, clopidogrel 300 mg was pre-administered 24 hours before concomitant administration of single doses of rivaroxaban 15 mg and clopidogrel 75 mg in healthy subjects. Clopidogrel with or without rivaroxaban led to an approximately 2-fold increase in the median bleeding time (normal range 2 - 8 minutes). In these studies, between 30% and 40% of subjects who received both rivaroxaban and clopidogrel had maximum bleeding times of up to 45 minutes. rivaroxaban alone did not lead to a change in bleeding time at 4 hours or 2 days after administration. There was no change in the pharmacokinetics of either drug. | Concomitant use with MINT-RIVAROXABAN increases the risk of bleeding. Promptly evaluate any signs or symptoms of blood loss (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions). |
| Concomitant Drug Class: Drug Name | Reference | Effect | Clinical comment |
Antithrombotic: enoxaparin | CT | After combined administration of enoxaparin (40 mg single dose) with rivaroxaban (10 mg single dose), an additive effect on anti-Factor-Xa activity was observed, without any additional effects on clotting tests (PT, aPTT). Enoxaparin did not affect the bioavailability and pharmacokinetics of rivaroxaban. | Co-administration of MINT-RIVAROXABAN at doses ≥10 mg with other anticoagulants or antithrombotic therapy has not been adequately studied in clinical trials. Due to the increased bleeding risk, generally avoid concomitant use with other anticoagulants (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions). |
| Selective serotonin reuptake inhibitors (SSRI), and serotonin norepinephrine reuptake inhibitors (SNRIs) | T, CT | When concomitantly used in the rivaroxaban clinical program, numerically higher rates of major or non-major clinically relevant bleeding were observed. | As with other anticoagulants, patients on MINT-RIVAROXABAN are at increased risk of bleeding in case of concomitant use with SSRIs or SNRIs due to their reported effect on platelets. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
No pharmacokinetic interaction was observed between warfarin and rivaroxaban.
There were no mutual pharmacokinetic interactions observed between rivaroxaban and midazolam (substrate of CYP 3A4), digoxin (substrate of P-gp), or atorvastatin (substrate of CYP 3A4 and P-gp).
Co-administration of the proton pump inhibitor, omeprazole, the H2-receptor antagonist, ranitidine, the antacid, aluminum hydroxide / magnesium hydroxide, or naproxen, clopidogrel, or enoxaparin did not affect rivaroxaban bioavailability or pharmacokinetics.
9.5 Drug-Food Interactions
MINT-RIVAROXABAN 10 mg may be taken with or without food. MINT-RIVAROXABAN 15 mg and 20 mg should be taken with food (see 10.3 Pharmacokinetics).
Grapefruit juice is a moderate CYP 3A4 inhibitor. Therefore, an increase in MINT-RIVAROXABAN exposure following grapefruit juice consumption is not expected to be clinically relevant.
9.6 Drug-Herb Interactions
The concomitant use of MINT-RIVAROXABAN with strong CYP 3A4 inducers (e.g, St. John’s Wort) may lead to a decreased rivaroxaban plasma concentration. Strong CYP 3A4 inducers should generally be avoided in combination with MINT-RIVAROXABAN, as such use can be expected to result in inadequate anticoagulation.
9.7 Drug-Laboratory Test Interactions
Although various clotting parameter tests (PT, aPTT, Heptest®) are affected by the mode of action of rivaroxaban, none of these clotting tests have been demonstrated to reliably assess the anticoagulant activity of rivaroxaban following rivaroxaban administration under usual conditions (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests, and 10.2 Pharmacodynamics).
The prothrombin time (PT), measured in seconds, is influenced by rivaroxaban in a dose- dependent way with a close correlation to plasma concentrations if the Neoplastin® reagent is used. In patients who are bleeding, measuring the PT (Neoplastin® reagent) in seconds, but not INR, may be useful to assist in determining an excess of anticoagulant activity (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
MINT-RIVAROXABAN (rivaroxaban) is a highly selective, direct, antithrombin independent Factor-Xa inhibitor with high oral bioavailability.
Activation of Factor-X to Factor-Xa (FXa) via the intrinsic and extrinsic pathway plays a central role in the cascade of blood coagulation. FXa directly converts prothrombin to thrombin through the prothrombinase complex and, ultimately, this reaction leads to fibrin clot formation and activation of platelets by thrombin. One molecule of FXa is able to generate more than 1000 molecules of thrombin due to the amplification nature of the coagulation cascade. In addition, the reaction rate of prothrombinase-bound FXa increases 300,000-fold compared to that of free FXa and causes an explosive burst of thrombin generation. Selective inhibitors of FXa can terminate the amplified burst of thrombin generation, thereby diminishing thrombin- mediated activation of coagulation.
10.2 Pharmacodynamics
There is a clear correlation between plasma rivaroxaban concentration and the degree of anticoagulant effect. The maximal effect (Emax) of rivaroxaban on pharmacodynamic parameters occurs at the same time as Cmax.
A dose-dependent inhibition of Factor-Xa (FXa) activity was observed over the complete dose range closely following the pharmacokinetic profiles which provides the ‘proof of mechanism’ in humans. Inhibition of FXa activity versus rivaroxaban plasma concentration follows a maximum effect (Emax) model. There is a close correlation between FXa inhibition and plasma concentrations with an r value of 0.97.
FXa assay tests require calibration and should not be used unless rivaroxaban-specific calibrators and controls are available.
- Prothrombin time (PT), measured in seconds, is influenced by rivaroxaban in a dose- dependent way with a close correlation to plasma concentrations (r = 0.98) if the Neoplastin® reagent is used. Other reagents would provide different results.
Although rivaroxaban therapy will lead to an elevated INR, depending on the timing of the measurement, the INR is not a valid measure to assess the anticoagulant activity of MINT-
- other anticoagulant (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
In patients who are bleeding, measuring the PT (Neoplastin® reagent) may be useful to assist in determining an excess of anticoagulant activity (see 7 WARNINGS AND PRECAUTIONS – Monitoring and Laboratory Tests).
Figure 1 and Figure 2 below show the relative measured effects of rivaroxaban 20 mg once daily for the PT test using the Neoplastin® reagent (Figure 1) and that expressed by the INR (Figure 2).
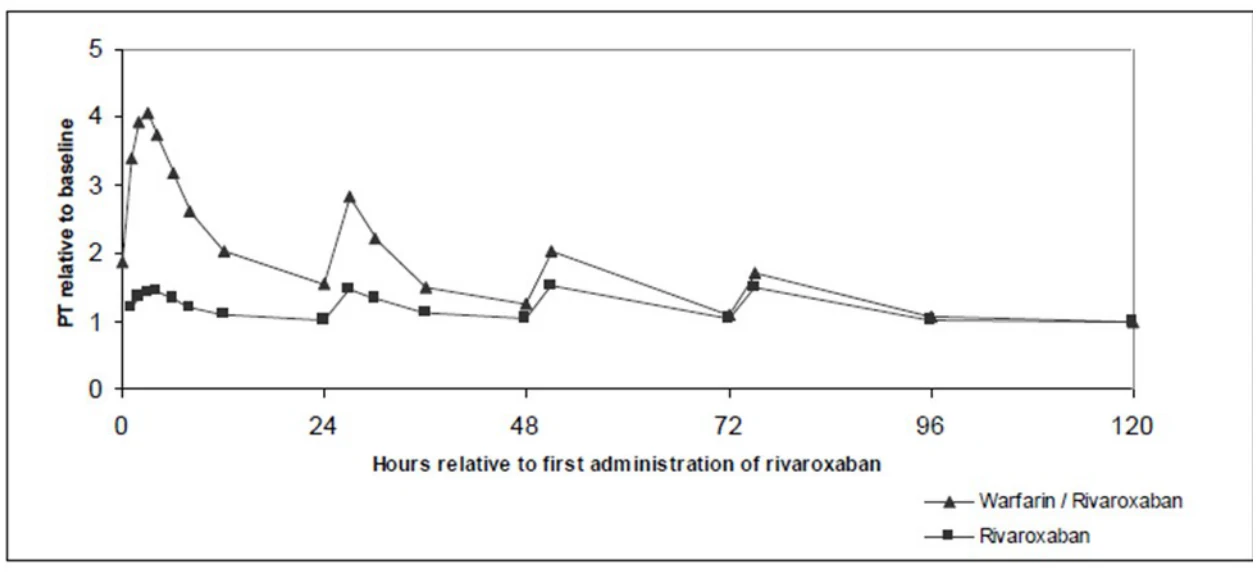
Figure 1: PT Prolongation (Neoplastin® reagent): Relative prolongation expressed as median of ratio to baseline with warfarin/rivaroxaban treatment and rivaroxaban alone, following last day of warfarin (Day -1) and 4 days of 20 mg rivaroxaban od, PD set, n=84
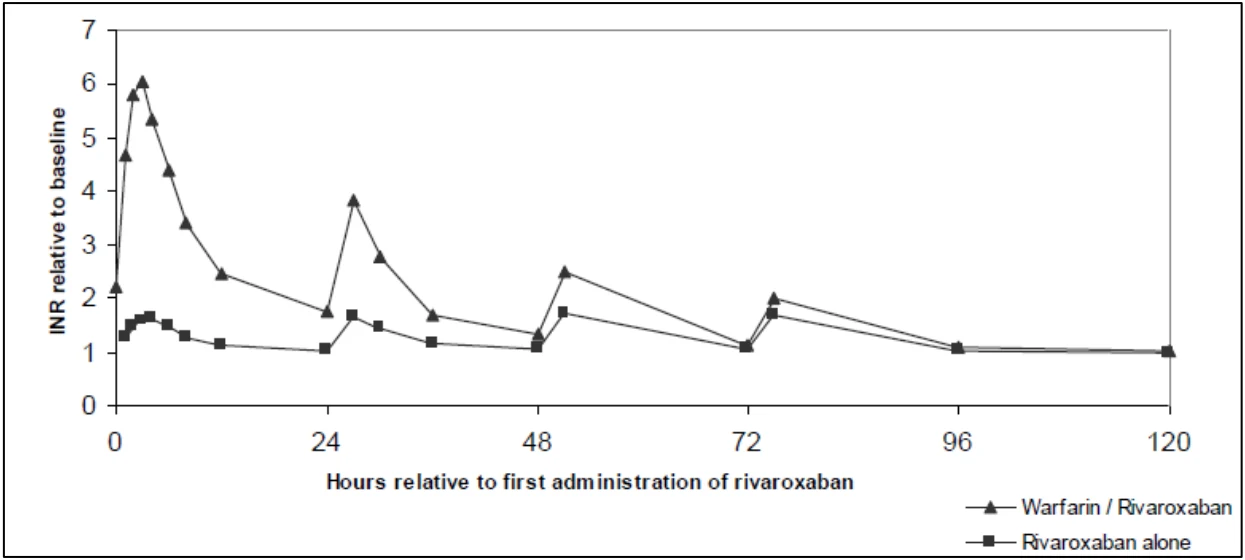
Figure 2: INR prolongation: Relative prolongation expressed as median of ratio to baseline with warfarin/ rivaroxaban treatment and rivaroxaban alone, following last day of warfarin
(Day -1) and 4 days of 20 mg rivaroxaban od, PK/PD set, n=84
The usual expected effect of rivaroxaban on PT when the Neoplastin® reagent is used is shown in Table 11 below.
Table 11 - PT (Neoplastin® reagent) by Indication, Following Rivaroxaban Administration
| Indication | Rivaroxaban Dosage | Plasma concentration Cmax (mcg/ L) | Plasma concentration Ctrough (mcg/L) | Range of (5/95 percentile) PT (Neoplastin®) Cmax | Range of (5/95 percentile) PT (Neoplastin®) Ctrough | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Prevention of VTE After THR or TKR | 10 mg od | 101 (7 – 273)a | 14 (4 – 51)c | 13 to 25 secondsa | 12-17 secondsc | ||||||||
| Treatment of VTE and Prevention of Recurrent DVT and PE | 15 mg bid | --- | --- | 17 to 32 secondsa | 14–24 secondsc | ||||||||
| 20 mg od | 215 (22– 535)a | 32 (6–239)d | 15 to 30 secondsa | 13–20 secondsd | |||||||||
Prevention of Stroke in Patients with Atrial Fibrillation | 15 mg od | 229 (178 – 313)b | 57 (18 – 136)e | 10 to 50 secondsb | 12–26 secondse | ||||||||
| 20 mg od | 249 (184 – 343)b | 44 (12 – 137)e | 14 to 40 secondsb | 11–26 secondse | |||||||||
a 2 to 4 hours after drug administration (tmax)
b 1 to 4 hours after drug administration (tmax)
c 8 to 16 hours after drug administration (tmin)
d 18 to 30 hours after drug administration (tmin)
e 16 to 32 hours after drug administration (tmin)
- The activated partial thromboplastin time (aPTT) is prolonged dose-dependently; however, the slope is rather flat and does not allow a sufficient discrimination at the relevant plasma concentrations. Therefore, aPTT is not considered to be adequate for following the pharmacodynamic effects. The r value for aPTT is 0.99.
- Heptest® is prolonged dose-dependently and correlates closely with plasma concentrations, following a curvilinear model. Despite the r value of 0.99 for the relation to plasma concentrations, the Heptest® is not considered optimal to assess the pharmacodynamic effects due to the curvilinear relationship.
QT Prolongation
No QTc prolonging effects were observed in healthy men and women older than 50 years. The treatment difference in QTcF 3 hours post-dose in comparison to placebo as well as QTcF, QTcI and QT analyses at the time of tmax and for post-dose changes in mean and maximum QTcF did not show any dose-related QTcF prolongation at both the 45 mg and the 15 mg dose of rivaroxaban. All changes in LS-means, including their 95% CI, were below 5 milliseconds.
Patients undergoing cardioversion
A prospective, randomized, open-label, multicenter, exploratory study with blinded endpoint evaluation (X-VeRT) was conducted in 1504 patients with non-valvular atrial fibrillation scheduled for cardioversion to compare rivaroxaban with dose-adjusted VKA (randomized 2:1). The rate of stroke occurring within 42 days of cardioversion was low and similar across treatment groups, i.e., rivaroxaban (0.20%) and VKA (0.41%). The rate of major bleeding was also low and similar across treatment groups, i.e., rivaroxaban (0.61%) and VKA (0.80%).
Patients with nonvalvular atrial fibrillation who undergo PCI with stent placement
In a randomized, open label, multicentre study (PIONEER AF-PCI) in patients with nonvalvular atrial fibrillation who underwent PCI with stent placement for primary atherosclerotic disease, the 12-month safety of two antithrombotic regimens was compared. One group of 696 patients received rivaroxaban 15 mg o.d. (10 mg o.d. in patients with CrCl 30-49 mL/min) in combination with a P2Y12 inhibitor (e.g, clopidogrel), while a second group of 697 patients received dose-adjusted VKA plus DAPT. Patients with a history of stroke or TIA were excluded from the trial.
The primary safety endpoint, clinically significant bleeding events [a composite of TIMI major bleeding, TIMI minor bleeding and Bleeding Requiring Medical Attention (BRMA)] occurred in 109 patients (15.7%) on the rivaroxaban regimen and in 167 patients (24.0%) on the VKA regimen (HR 0.59; 95% CI 0.47-0.76; p<0.001). This difference in bleeding risk was primarily a result of significantly fewer BRMA events in patients on the rivaroxaban regimen. While a consistent treatment effect for all 3 components of the composite was observed, the low number of TIMI major and TIMI minor bleeding events during the trial prevented the demonstration of a significant difference between the two regimens for these endpoints. The secondary endpoint, a composite of CV death, MI or stroke, occurred in 41 patients (5.9%) on rivaroxaban and in 36 patients (5.2%) on VKA; stent thrombosis occurred in 5 patients on rivaroxaban and in 4 patients on VKA. The study was not designed to compare efficacy between the treatment arms, preventing any conclusions regarding efficacy.
10.3 Pharmacokinetics
Rivaroxaban pharmacokinetics are linear with no relevant accumulation beyond steady state after multiple doses. Variability in pharmacokinetics is moderate with interindividual variability (coefficient of variation) ranging from 30% to 40%.
Absorption
Rivaroxaban is a low solubility, high permeability compound. Rivaroxaban is readily absorbed after oral administration as solution (Cmax after approximately 30 min) as well as tablet (Cmax after 2 to 4 hours). Oral bioavailability of rivaroxaban is high (80-100%) due to almost complete absorption with/without food (at doses up to 15 mg) and lack of relevant presystemic first-pass extraction of this low-clearance drug.
The following information is based on the data obtained in adults.
The absolute bioavailability of rivaroxaban is approximately 100% for doses up to 10 mg. Rivaroxaban is rapidly absorbed with maximum concentrations (Cmax) appearing 2 to 4 hours after tablet intake.
Intake with food does not affect rivaroxaban AUC or Cmax for doses up to 10 mg. MINT-RIVAROXABAN 10 mg tablets can be taken with or without food. Due to reduced extent of absorption an oral bioavailability of 66% was determined for the 20 mg tablet under fasting conditions. When rivaroxaban 20 mg tablets are taken together with food, increases in mean AUC by 39% and mean Cmax by 76% were observed when compared to tablet intake under fasting conditions, indicating almost complete absorption and high oral bioavailability when this dose was taken with food.
The bioavailability of rivaroxaban 10 mg, 15 mg and 20 mg tablets under fed conditions, and 10 mg tablets under fasted conditions, demonstrated dose-proportionality. MINT-RIVAROXABAN 15 mg and 20 mg tablets should be taken with food (see 4 DOSAGE AND ADMINISTRATION).
Rivaroxaban pharmacokinetic parameters behave in a linear fashion; no evidence of undue accumulation beyond steady-state was seen after multiple doses.
Interindividual variability (CV%) of rivaroxaban pharmacokinetics ranges from 30% to 40%. This may be increased on the day of surgery and on the following day when interindividual variability is 70%.
Table 12 - Summary of PK Parameters After Oral Administration of 10 mg of Rivaroxaban in Humans
Cmax [µg/L] | t1/2 [h] | AUC [µg*h/L] | Clearance, Urinary Excretion | Volume of Distribution | |
|---|---|---|---|---|---|
| Healthy (Young) Subjects | Approx. 114a | 5-9 | Approx. 817 | CLsys = approx. 10 L/h CLR = 3 – 4 L/h Aeur = 30% - 40% | Vss = approx. 50 L |
| Patients | Approx. 125 | 7-11 | Approx. 1170 | N/A (no IV data) b Aeur = 22% | N/A (no IV data) |
a = 2 – 4 hours after drug administration (tmax) b = not available
AUC = area under the plasma-concentration time curve; Aeur = amount of drug excreted unchanged into urine; CLsys = systemic clearance (after intravenous administration); CLR = renal clearance; Cmax = maximum plasma concentration; t 1/2 = terminal elimination half-life; tmax = time to reach Cmax; Vss = volume of distribution at steady state
Absorption of rivaroxaban is dependent on the site of drug release in the GI tract. A 29% and 56% decrease in AUC and Cmax compared to orally ingested tablet was reported when rivaroxaban granulate is released in the proximal small intestine. Exposure is further reduced when drug is released in the distal small intestine, or ascending colon. Avoid administration of rivaroxaban distal to the stomach as this can result in reduced absorption and related drug exposure.
In an open-label, randomized, 3-period, 3-treatment crossover comparative bioavailability study conducted in 44 healthy male and female subjects, the bioavailability (AUCT and Cmax) of rivaroxaban following a single 20 mg dose as a crushed 20 mg tablet mixed in applesauce and administered orally, or as a crushed 20 mg tablet suspended in water and administered via NG tube was comparable to a whole 20 mg tablet administered orally. Each rivaroxaban treatment was taken with a standardized liquid meal. Given, the predictable, dose-proportional pharmacokinetic profile of rivaroxaban, the bioavailability results from this study are likely applicable to lower rivaroxaban doses.
Distribution
Plasma protein binding for rivaroxaban in humans is high at approximately 92% to 95% in vitro, with serum albumin being the main binding component. No concentration dependency and no gender difference in fraction unbound were detected. Mean rivaroxaban protein-bound fractions determined ex vivo in healthy subjects ranged from 90% to 95%. The volume of distribution is moderate with Vss being approximately 50 L.
Due to its high plasma protein binding, rivaroxaban is not expected to be removed by dialysis.
The binding of rivaroxaban to plasma proteins is fully reversible. In accordance with other species, rivaroxaban is mainly located in plasma; the human plasma-to-blood partition coefficient is 1.40.
Metabolism
Rivaroxaban is eliminated by metabolic degradation (approximately 2/3 of administered dose) as well as by direct renal excretion of unchanged active compound (approximately 1/3 of administered dose). In all investigated species, the oxidative degradation of the morpholinone moiety (catalyzed via CYP 3A4/CYP 3A5 and CYP 2J2 and leading via cleavage of the ring and further oxidation to metabolite M-1) was the major site of biotransformation of rivaroxaban. Unchanged rivaroxaban is the most important compound in human plasma with no major or active circulating metabolites being present. No metabolic conversion of rivaroxaban to its enantiomer was observed in humans.
Taking excretion data and metabolite profiles derived from the mass balance study in man into consideration, present data from the CYP reaction phenotyping study suggests that contribution of CYP 3A4/CYP 3A5 accounts for approximately 18% and CYP 2J2 for approximately 14% of total rivaroxaban elimination, respectively. Besides this oxidative biotransformation, hydrolysis of the amide bonds (approximately 14%) and active, transporter-mediated renal excretion of unchanged drug (approximately 30%) play important roles as elimination pathways.
Elimination
Rivaroxaban and its metabolites have a dual route of elimination, via both renal (66% in total) and biliary/fecal routes; 36% of the administered dose is excreted unchanged via the kidneys via glomerular filtration and active secretion.
The clearance and excretion of rivaroxaban is as follows:
- 1/3 of the active drug is cleared as unchanged drug by the kidneys
- 1/3 of the active drug is metabolized to inactive metabolites and then excreted by the kidneys
- 1/3 of the active drug is metabolized to inactive metabolites and then excreted by the fecal route.
Rivaroxaban has been identified in vitro to be a substrate both of the active transporter P-glycoprotein (P-gp) and of the multidrug transport protein BCRP (‘breast cancer resistance protein’).
With an average systemic plasma clearance of approximately 10 L/h, rivaroxaban is a low- clearance drug lacking relevant first-pass extraction. Mean terminal elimination half-lives of rivaroxaban are in the range of 5 h to 9 h after steady-state tablet dosing regimens in young subjects. Mean terminal elimination half-lives between 11 h to 13 h were observed in the elderly.
Special Populations and Conditions
Geriatrics (> 65 Years of Age)
Clinical studies have been conducted in older ages, with results of prolonged terminal half-lives (11 to 13 hours in elderly versus 5 to 9 hours in young subjects) accompanied by increases of rivaroxaban exposure (approximately 50%) compared to young healthy subjects. This difference may be due to reduced renal function in the elderly (see 2 CONTRAINDICATIONS, 7 WARNINGS AND PRECAUTIONS – Renal Impairment, and 4 DOSAGE AND ADMINISTRATION – Renal Impairment).
Results from a set of Phase I studies indicate for the target population of elderly higher mean AUC values by 52% in males and by 39% in females when compared to young subjects of the same gender, accompanied by an increase in Cmax by 35% in both genders and by terminal half- lives between 11 and 13 h. Investigating subjects older than 75 years confirmed the expectation, leading to approximately 41% higher AUC values in comparison to young subjects (90% CI [1.20 – 1.66]), mainly due to reduced
(apparent) total body clearance and renal clearance. No relevant age effects could be observed for Cmax (Cmax ratio 1.08; 90% CI [0.94-1.25]) or tmax
Sex
There were no clinically relevant differences in pharmacokinetics and pharmacodynamics between male and female subjects, especially when taking into account body weight differences.
Body Weight
In adults, extremes in body weight (<50 kg vs >120 kg) had only a small influence on rivaroxaban plasma concentrations (less than 25%).
Ethnic Origin
In adults, no clinically relevant interethnic differences among Caucasian, African-American, Hispanic, Japanese or Chinese patients were observed regarding pharmacokinetics and pharmacodynamics.
Hepatic Insufficiency
A Phase I study in adults investigated the influence of impaired hepatic function in cirrhotic patients (Child-Pugh Class A or B, number of patients 8 per group) on the pharmacodynamics and pharmacokinetics of a single dose of rivaroxaban.
In patients with mild hepatic impairment (Child-Pugh Class A), there was no difference as compared to healthy volunteers with respect to either pharmacodynamics (inhibition of Factor- Xa activity [1.08-fold for AUC and 0.98-fold for Emax]), prolongation of prothrombin time (1.02-fold for AUC and 1.06-fold for Emax), or pharmacokinetics (both total and unbound AUC [1.15 for total and 0.91-fold increase for unbound] and Cmax [0.97 for total and 0.78-fold for unbound]).
Child-Pugh Class B patients had lower baseline Factor-Xa activity levels (0.64 U/mL) compared to healthy subjects and Child-Pugh Class A patients (0.85 U/mL, for both patient populations). Inhibition of Factor-Xa activity was more pronounced in Child-Pugh Class B patients compared to both healthy subjects and Child-Pugh Class A patients. The increase of inhibition was 2.6-fold AUC(0-tn) and 1.2-fold maximal effect (Emax). The group difference was statistically significant, both for AUC(0-tn) (P < 0.01) as well as for Emax (P < 0.05) of inhibition of Factor-Xa activity. In line with these results, a relevant difference in prolongation of PT was observed between healthy subjects and Child-Pugh Class B patients. The increase of prolongation was 2.1-fold (AUC(0-tn)) and 1.4-fold (Emax). A statistically significant group-difference was observed for AUC(0 tn) (P <0.0004) as well as Emax (P <0.0001).
Pharmacokinetic parameters also indicated a significant increase in Child-Pugh Class B patients as compared to healthy volunteers both on AUC pharmacokinetics (both total and unbound AUC [2.27-fold for total and 2.57-fold increase for unbound]) and Cmax (1.27-fold for total and 1.38-fold for unbound).
A PK/PD analysis showed that the slope of the prothrombin time/plasma concentration correlation is increased by more than 2-fold for Child-Pugh Class B patients as compared to healthy volunteers. Since the global clotting test PT assesses the extrinsic pathway that is comprised of the coagulation Factor-VII, Factor-X, Factor-V, Factor-II, and Factor-I which are synthesized in the liver, impaired liver function can also result in prolongations of PT in the absence of anticoagulant therapy.
The PK/PD changes observed in Child-Pugh Class B patients are markers for the severity of the underlying hepatic disease which is expected to lead to a subsequent increased bleeding risk in this patient group.
MINT-RIVAROXABAN is contraindicated in patients with hepatic disease (including Child-Pugh Class B and C) associated with coagulopathy, and having clinically relevant bleeding risk (see 2 CONTRAINDICATIONS, and 7 WARNINGS AND PRECAUTIONS – Hepatic Impairment).
The safety and pharmacokinetics of single-dose rivaroxaban (10 mg) were evaluated in a study in healthy subjects (n=16) and subjects with varying degrees of hepatic impairment (see Table 13). No patients with severe hepatic impairment (Child-Pugh C) were studied. Compared to healthy subjects with normal liver function, significant increases in rivaroxaban exposure were observed in subjects with moderate hepatic impairment (Child-Pugh B). Increases in pharmacodynamic effects were also observed.
Table 13 - Percent Increase of Rivaroxaban PK and PD Parameters from Normal in Subjects with Hepatic Insufficiency from a Dedicated Hepatic Impairment Study
| Parameter | Hepatic Impairment Class (Child-Pugh Class) | ||
|---|---|---|---|
Mild (Child-Pugh A) | Moderate (Child-Pugh B) | ||
| N=8 | N=8 | ||
Exposure (% increase relative to normal) | AUC | 15 | 127 |
| Cmax | 0 | 27 | |
FXa Inhibition (% increase relative to normal) | AUC | 8 | 159 |
| Emax | 0 | 24 | |
PT Prolongation (% increase relative to normal) | AUC | 6 | 114 |
| Emax | 2 | 41 | |
PT = Prothrombin time; FXa = Coagulation factor Xa; AUC = Area under the concentration or effect curve; Cmax= maximum concentration; Emax = maximum effect; and CrCl = creatinine clearance
Renal Insufficiency
As active rivaroxaban is partially cleared via the kidneys (30% to 40% of the dose), there is a direct but moderate correlation of systemic exposure to rivaroxaban with degree of renal impairment.
In a Phase I study in adults, following oral single dosing with rivaroxaban 10 mg in subjects with mild (CrCl 50 – 79 mL/min), moderate (CrCl 30 – 49 mL/min), or severe (CrCl 15 – 29 mL/min) renal impairment, rivaroxaban plasma concentrations (AUC) were increased 1.4-, 1.5-, and 1.6-fold, respectively compared to healthy subjects with normal renal function (CrCl ≥ 80 mL/min).
The overall inhibition of Factor-Xa activity (AUC(0-48h) of effect versus time) was increased in these groups by a factor of 1.5, 1.9, and 2.0, respectively. The relative prolongation of prothrombin time (PT) was also affected by renal impairment and showed even more pronounced effects. AUC(0-48h) of effect versus time was increased by a factor of 1.3, 2.2, and 2.4, respectively.
In Phase II, rivaroxaban plasma concentrations (AUC) were increased 1.2- and 1.5-fold in subjects with mild and moderate renal impairment respectively compared to healthy subjects with normal renal function and the peak inhibition of Factor-Xa activity (AUC(0-48h) of effect versus time) was increased in these groups by a factor of 1.0 and 1.3 respectively. In a pooled analysis of Phase III THR or TKR subjects with mild and moderate renal impairment, the peak PT was increased by 1.0-, and 1.1-fold compared to subjects with normal renal function.
In Phase II (VTE treatment), rivaroxaban plasma concentrations (AUC) were 1.3- and 1.5-fold in subjects with mild and moderate renal impairment, respectively, compared to subjects with normal renal function. In Phase III subjects (VTE treatment) with mild renal impairment, the peak PT was increased by 1.1-fold, and 1.2-fold for moderate renal impairment compared to subjects with normal renal function.
In patients with atrial fibrillation evaluated in Phase III, the peak PT was increased by 1.2-fold for both mild and moderate renal impairment compared to subjects with normal renal function.
There was no evidence of substantial drug accumulation in patients with mild or moderate renal impairment.
The safety and pharmacokinetics of single-dose rivaroxaban (10 mg) were evaluated in a study in healthy subjects [CrCl ≥80 mL/min (n=8)] and in subjects with varying degrees of renal impairment (see Table 14). Compared to healthy subjects with normal creatinine clearance, rivaroxaban exposure increased in subjects with renal impairment. Increases in pharmacodynamic effects were also observed.
Table 14 - Percent Increase of Rivaroxaban PK and PD Parameters from Normal in Subjects with Renal Insufficiency from a Dedicated Renal Impairment Study
| Parameter | CrCl (mL/min) | |||
|---|---|---|---|---|
| 50 to 79 | 30 to 49 | 15 to 29 | ||
| N=8 | N=8 | N=8 | ||
Exposure (% increase relative to normal) | AUC | 44 | 52 | 64 |
| Cmax | 28 | 12 | 26 | |
FXa Inhibition (% increase relative to normal) | AUC | 50 | 86 | 100 |
| Emax | 9 | 10 | 12 | |
PT Prolongation (% increase relative to normal) | AUC | 33 | 116 | 144 |
| Emax | 4 | 17 | 20 | |
PT = Prothrombin time; FXa = Coagulation factor Xa; AUC = Area under the concentration or effect curve;
Cmax = maximum concentration; Emax = maximum effect; and CrCl = creatinine clearance
In subjects with mild renal impairment, the combined P-gp and moderate CYP 3A4 inhibitor erythromycin (500 mg three times a day) led to a 1.8-fold increase in mean rivaroxaban AUC and 1.6-fold increase in Cmax when compared to subjects with normal renal function without co- medication. In subjects with moderate renal impairment, erythromycin led to a 2.0-fold increase in mean rivaroxaban AUC and 1.6-fold increase in Cmax when compared to subjects with normal renal function without co-medication (see 7 WARNINGS AND PRECAUTIONS – Drug Interactions). Subjects with either mild or moderate renal impairment had a 1.2- and 1.4-fold increase in Factor Xa inhibition, respectively, and a prolongation of prothrombin time of 1.7- and 1.75-fold in subjects with mild and moderate renal impairment, respectively.
11 STORAGE, STABILITY AND DISPOSAL
Store MINT-RIVOROXABAN film-coated tablets at 15°C to 30°C.
Store in a safe place out of the reach of children.
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are required for this product.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Rivaroxaban
Chemical name: (S)-5-Chloro-N-((2-oxo-3-(4-(3-oxomorpholino)phenyl) oxazolidin-5-yl) methyl) thiophene-2-carboxamide
Molecular formula and molecular mass: C19 H18 Cl N3 O5 S
435.89 g/mol
Structural formula:
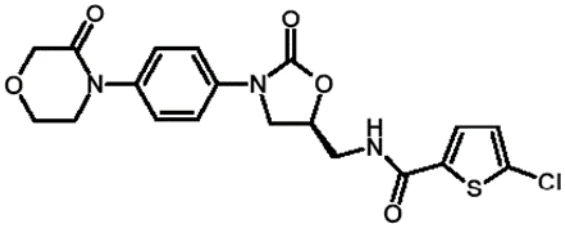
Physicochemical properties: Rivaroxaban is a pure (S)-enantiomer. It is a nonhygroscopic, white to yellowish powder. Rivaroxaban is very slightly soluble to practically insoluble in acetone and water at temperature 25°C ± 2°C
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Prevention of VTE after THR or TKR
Table 15 - Summary of the Pivotal Studies for the Prevention of Venous Thromboembolic Events (VTE) in Patients Undergoing Elective Total Hip Replacement (THR) or Total Knee Replacement (TKR) Surgery
| Study | Study Design | Treatment Regimen | Patient Populations |
|---|---|---|---|
| RECORD 1a | Rivaroxaban 10 mg od oral for 35±4 days (first dose administered 6 to 8 h postoperatively) Enoxaparin 40 mg od SC for 36±4 days (first dose administered 12 h preoperatively) | Randomized 4541 (2266 rivaroxaban, 2275 enoxaparin) Safety Population 4433 (2209 rivaroxaban, 2224 enoxaparin) mITT 3153 (1595 rivaroxaban, 1558 enoxaparin) mITT (for Major VTE) 3364 (1686 rivaroxaban, 1678 enoxaparin) Per Protocol 3029 (1537 rivaroxaban, 1492 enoxaparin) | |
| RECORD 3a | Rivaroxaban 10 mg od oral for 12±2days (first dose administered 6 to 8 h postoperatively) Enoxaparin 40 mg od SC for 13±2 days (first dose administered 12 h preoperatively) | Randomized 2531 (1254 rivaroxaban, 1277 enoxaparin) Safety Population 2459 (1220 rivaroxaban, 1239 enoxaparin) mITT 1702 (824 rivaroxaban, 878 enoxaparin) mITT (for Major VTE) 1833 (908 rivaroxaban, 925 enoxaparin) Per Protocol 1631 (793 rivaroxaban, 838 enoxaparin) |
a The mean age of patients in RECORD 1 and 3 was 63.2±11.4, and 67.6±9 years, respectively.
Safety population = The safety population comprised those patients who received at least 1 dose of study drug. mITT = A subject was considered valid for the modified intent-to-treat (MITT) analysis if the subject was (1) valid for safety analysis; (2) had undergone the appropriate surgery; and (3) had an adequate assessment of thromboembolism.
mITT (for Major VTE) = A subject was valid for MITT analysis of major VTE, if the subject was (1) valid for safety analysis; (2) had undergone the appropriate surgery; and (3) had an adequate assessment of thromboembolism for major VTE.
Per Protocol = the per-protocol (PP) population was to include patients who were (1) valid for the MITT analysis; (2) had an adequate assessment of thromboembolism that, in case of a positive finding, was done not later than 36 h after stop of active study drug, in case of no finding, was done not later than 72 h after the end of active study drug; and (3) had no major protocol deviations.
Major VTE = composite of proximal DVT, nonfatal PE, or VTE-related death
od = once daily
SC = subcutaneous
The pivotal studies were designed to demonstrate the efficacy of rivaroxaban for the prevention of venous thromboembolic events (VTE), i.e., proximal and distal deep vein thrombosis (DVT) and pulmonary embolism (PE) in patients undergoing elective total hip replacement (THR) or total knee replacement (TKR) surgery. A once daily dose of 10 mg was selected for all Phase III studies in the prevention of VTE in patients undergoing THR or TKR surgery, based on clinical data generated in Phase II studies. Over 9,500 patients (7,050 in THR surgery; 2,531 in TKR surgery) were studied in these controlled randomized double-blind studies (RECORD 1, 2, and 3).
Pivotal Studies
The RECORD 1 and 3 studies were multicenter, multinational, prospective, double-blind, double-dummy studies in patients randomized to rivaroxaban or to enoxaparin, see Table 15. A non-inferiority was adopted with the pre-specification that, if non-inferiority was shown, a second analysis would be undertaken to determine if the efficacy of rivaroxaban was superior to that of enoxaparin. RECORD 1 was conducted in patients undergoing elective THR surgery while RECORD 3 was conducted in patients undergoing elective TKR surgery. In both studies, rivaroxaban 10 mg once daily started not earlier than 6 hours postoperatively was compared with an enoxaparin dosage regimen of 40 mg once daily started 12 hours preoperatively, as recommended in many countries worldwide. The dose of enoxaparin sodium approved for use in thromboprophylaxis in conjunction with elective THR or TKR surgery in Canada is subcutaneous 30 mg twice daily with the first dose to be administered 12 to 24 hours postoperatively. The primary endpoint was Total VTE a composite of any DVT (distal or proximal), nonfatal PE, or death from any cause. The main secondary endpoint was Major VTE, a composite endpoint comprising proximal DVT, nonfatal pulmonary embolism (PE), and VTE-related death. Other pre-specified secondary efficacy endpoints included the incidence of DVT (any thrombosis, including proximal and distal) and the incidence of symptomatic VTE.
Men and women of 18 years or older scheduled for elective surgery could be enrolled provided that they had no active or high risk of bleeding or other conditions contraindicating treatment with low-molecular-weight heparin, no significant liver disease, were not pregnant or breastfeeding women, or were not using HIV-protease inhibitors.
In RECORD 1 and 3, demographic and surgical characteristics were similar between the two groups except for a significantly larger number of females in RECORD 3 (rivaroxaban 70% and enoxaparin 66%, P = 0.03). The reasons for exclusion of patients from various analyses in both studies were also similar.
The results of the non-inferiority analysis of Total VTE for RECORD 1 and 3 are presented in Table 16. For the primary efficacy analysis, the difference between the incidences in the rivaroxaban group and the enoxaparin group were estimated, after stratification according to country using the Mantel-Haenszel weighting, and the corresponding asymptotic two-sided 95% confidence interval was determined. Tests for non-inferiority and superiority were both based on the 95% confidence interval. Non-inferiority was shown if the lower limit of the CI was above the pre-specified non-inferiority margin; -3.5% in RECORD 1 and -4% in RECORD 3.
Table 16 - RECORD 1 (THR) and RECORD 3 (TKR): Non-inferiority Analysis of Total VTEa, the Primary Composite Efficacy Endpoint, and its Components –Per Protocol (PP)b Population Through the Double-Blind Treatment Period
| RECORD 1 (THR) | RECORD 3 (TKR) | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Rivaroxaban 10 mg od N=1537 n (%) | Enoxaparin 40 mg od N=1492 n (%) | Rivaroxaban 10 mg od N=793 n (%) | Enoxaparin 40 mg od N=838 n (%) | |||||||||||
| Total VTEa (primary composite endpoint) | 13 (0.9%) | 50 (3.4%) | 74 (9.3%) | 152 (18.1%) | ||||||||||
Absolute Risk Reductionc 2.5% (1.5% to 3.6%; P <0.001) | Absolute Risk Reductionc 8.7% (5.4% to 12.0%; P <0.001) | |||||||||||||
| DVT (proximal and/or distal) | 11 (0.7) | 47 (3.2) | 74 (9.3) | 147 (17.5) | ||||||||||
| Nonfatal PE | 2 (0.1) | 1 (<0.1) | 0 | 3 (0.4) | ||||||||||
| Death from all causes | 1 (<0.1) | 2 (0.1) | 0 | 2 (0.2) | ||||||||||
- a Total VTE = DVT (proximal and/or distal), nonfatal PE, or death from all causes
- b
PP = the per-protocol (PP) population was to include patients who were (1) valid for the MITT analysis;
(2) had an adequate assessment of thromboembolism that, in case of a positive finding, was done not later than 36 h after stop of active study drug, in case of no finding, was done not later than 72 h after the end of active study drug; and (3) had no major protocol deviations
- c Mantel-Haenszel Weighted Reduction to Enoxaparin (Non-inferiority was shown if the lower limit of the CI was above the pre-specified non-inferiority margin; -3.5% in RECORD 1 and -4% in RECORD 3)
In both pivotal studies, the per-protocol analysis for the primary endpoint showed that rivaroxaban 10 mg od/day (first dose 6 to 8 hours postoperatively) was not inferior to enoxaparin 40 mg/day (first dose 12 to 24 hours preoperatively).
Since non-inferiority was shown, a pre-specified superiority analysis was undertaken to determine if the efficacy of rivaroxaban was superior to that of enoxaparin in the modified intent- to-treat population (mITT). The superiority analysis of Total VTE and data for the main secondary endpoint (Major VTE) and other secondary endpoints for RECORD 1 and 3 are presented in Table 17 and Table 18, respectively.
Table 17 - RECORD 1 (THR): Superiority Analysis for Total VTE (Primary Composite Endpoint)a, Major VTE (Main Secondary Endpoint)b and Their Components, and Other Selected Efficacy Endpoints – Modified ITTc (MITT) Population Through the Double-Blind Treatment Period a Total VTE = composite of DVT (proximal and/or distal), nonfatal PE, or death from all causes.
b Major VTE = composite of proximal DVT, nonfatal PE, or VTE-related death
- c MITT = subject valid for safety analysis, has undergone appropriate surgery, has adequate assessment of thromboembolism
- d Mantel-Haenszel Weighted Reduction to Enoxaparin given for all endpoints except nonfatal PE and death from all causes, for which unweighted (exact) estimates were given. Superiority was shown if the lower limit of the CI was above zero.
- e Safety population for Symptomatic VTE (patients valid for safety analysis who underwent the appropriate surgery). The safety population was used because assessment of symptomatic events is possible in the greater population, regardless of the availability of an adequate venographic assessment.
| Parameter | Rivaroxaban 10 mg | Enoxaparin 40 mg | Absolute Risk Reductiond | P-Value | Relative Risk Reduction | P-Value | ||
|---|---|---|---|---|---|---|---|---|
| n/N | % (95% CI) | n/N | % (95% CI) | % (95% CI) | % (95% CI) | |||
| Total VTE | 18/1595 | 1.1% (0.7% to 1.8%) | 58/1558 | 3.7% (2.8% to 4.8%) | 2.6% (1.5% to 3.7%) | <0.001 | 70% (49%-82%) | P <0.001 |
| Major VTE | 4/1686 | 0.2% (0.1% to 0.6%) | 33/1678 | 2.0% (1.4% to 2.8%) | 1.7% (1.0% to 2.5%) | <0.001 | 88% (66%-96%) | P <0.001 |
| Death from all causes | 4/1595 | 0.3% (0.1% to 0.6%) | 4/1558 | 0.3% (0.1% to 0.7%) | 0.0% (-0.4% to 0.4%) | 1.00 | -- | -- |
| Nonfatal PE | 4/1595 | 0.3% (0.1% to 0.6%) | 1/1558 | 0.1% (<0.1% to 0.4%) | -0.2% (-0.6% to 0.1%) | 0.37 | -- | -- |
| DVT (proximal and/or distal) | 12/1595 | 0.8% (0.4% to 1.3%) | 53/1558 | 3.4% (2.6% to 4.4%) | 2.7% (1.7% to 3.7%) | <0.001 | -- | -- |
| Proximal DVT | 1/1595 | 0.1% (<0.1% to 0.4%) | 31/1558 | 2.0% (1.4% to 2.8%) | 1.9% (1.2% to 2.7%) | <0.001 | -- | -- |
| Distal DVT only | 11/1595 | 0.7% (0.3% to 1.2%) | 22/1558 | 1.4% (0.9% to 2.1%) | 0.7% (0.0% to 1.5%) | 0.04 | -- | -- |
| VTE-related death | 0/1595 | 0% | 1/1558 | <0.1% | -- | -- | -- | -- |
| Symptomatic VTEe | 6/2193 | 0.3% (0.1% to 0.6%) | 11/2206 | 0.5% (0.3% to 0.9%) | 0.2% (-0.1% to 0.6%) | 0.22 | -- | -- |
Table 18 - RECORD 3 (TKR): Superiority Analysis for Total VTE (Primary Composite Endpoint)a, Major VTE (Main Secondary Endpoint)b and Their Components, and Other Selected Efficacy Endpoints – Modified ITT (MITT)c Population Through the Double-Blind Treatment Period
| Parameter | Rivaroxaban 10 mg | Enoxaparin 40 mg | Absolute Risk Reductiond | P-Value | Relative Risk Reduction | P-Value | ||
|---|---|---|---|---|---|---|---|---|
| n/N | % (95% CI) | n/N | % (95% CI) | % (95% CI) | % (95% CI) | |||
| Total VTE | 79/824 | 9.6% (7.7% to 11.8%) | 166/878 | 18.9% (16.4% to 21.7%) | 9.2% (5.9% to 12.4%) | <0.001 | 49% (35%-61%) | <0.001 |
| Major VTE | 9/908 | 1.0% (0.5% to 1.9%) | 24/925 | 2.6% (1.7% to 3.8%) | 1.6% (0.4% to 2.8%) | 0.01 | 62% (18%-82%) | 0.016 |
| Death from all causes | 0/824 | 0% (0.0% to 0.5%) | 2/878 | 0.2% (0.0% to 0.8%) | 0.2% (-0.2% to 0.8%) | 0.23 | -- | -- |
| Nonfatal PE | 0/824 | 0% (0.0% to 0.3%) | 4/878 | 0.5% (0.1% to 1.2%) | 0.5% (0.0% to 1.2%) | 0.06 | -- | -- |
| DVT (proximal and/or distal) | 79/824 | 9.6% (7.7% to 11.8%) | 160/878 | 18.2% (15.7% to 20.9%) | 8.4% (5.2% to 11.7%) | <0.001 | -- | -- |
| Proximal DVT | 9/824 | 1.1% (0.5% to 2.1%) | 20/878 | 2.3% (1.4% to 3.5%) | 1.1% (-0.1% to 2.3%) | 0.07 | -- | -- |
| Distal DVT only | 70/824 | 8.5% (6.7% to 10.6%) | 140/878 | 15.9% (13.6% to 18.5%) | 7.3% (4.3% to 10.4%) | <0.001 | -- | -- |
| VTE-related death | 0/824 | 0% | 0/878 | 0% | -- | -- | -- | -- |
| Symptomatic VTEe | 8/1201 | 0.7% (0.3% to 1.3%) | 24/1217 | 2.0% (1.3% to 2.9%) | 1.3% (0.4% to 2.2%) | 0.005 | -- | -- |
a Total VTE = composite of DVT (proximal and/or distal), nonfatal PE, or death from all causes.
b Major VTE = composite of proximal DVT, nonfatal PE, or VTE-related death
- c MITT = subject valid for safety analysis, has undergone appropriate surgery, has adequate assessment of thromboembolism
- d Mantel-Haenszel Weighted Reduction to Enoxaparin given for all endpoints except nonfatal PE and death from all causes, for which unweighted (exact) estimates were given. Superiority was shown if the lower limit of the CI was above zero.
- e Safety population for Symptomatic VTE (patients valid for safety analysis who underwent the appropriate surgery). The safety population was used because assessment of symptomatic events is possible in the greater population, regardless of the availability of an adequate venographic assessment.
The efficacy results of the pre-specified analysis using a modified intent-to-treat population indicate that rivaroxaban 10 mg administered postoperatively once daily is superior in preventing DVT to enoxaparin 40 mg once daily (first dose 12 hours preoperatively). The Canadian approved dosage regimen for enoxaparin is 30 mg every 12 hours (first dose is to be administered 12 to 24 hours postoperatively). There are no definitive head-to-head studies to compare the safety and efficacy of the Canadian approved enoxaparin dosage regimen to the enoxaparin dosage regimen used in the RECORD 1 and 3 studies.
In the safety population of 3429 patients treated with rivaroxaban and 3463 patients treated with enoxaparin in the pivotal studies (RECORD 1 and 3), the results observed for bleeding events have been summarized in Table 19. In RECORD 1, serious drug-related treatment-emergent adverse events were reported in 26 (1.2%) for rivaroxaban and 23 (1.0%) for enoxaparin. In RECORD 3, serious drug-related treatment-emergent adverse events were reported in 26 (2.1%) for rivaroxaban and 19 (1.5%) for enoxaparin.
Table 19 - RECORD 1 and 3: Detailed Overview of Treatment-Emergent Bleeding Events (Safety Population)a
| RECORD 1 (THR) | RECORD 3 (TKR) | |||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Rivaroxaban 10 mg od N=2209 | Enoxaparin 40 mg od N=2224 | P-Value | Rivaroxaban 10 mg od N=1220 | Enoxaparin 40 mg od N=1239 | P-Value | |||||||||||||
Any Bleeding n (%)(95% CI) | 133 (6.0%) (5.1% to 7.1%) | 131 (5.9%) (5.0% to 7.0%) | 0.90 | 60 (4.9%) (3.8%-6.3%) | 60 (4.8%) (3.7%-6.2%) | 1.0 | ||||||||||||
Major Bleedingb n (%) (95% CI) | 6 (0.3%) (0.1%-0.6%) | 2 (0.1%) (<0.1%-0.3%) | 0.18 | 7 (0.6%) (0.2%-1.2%) | 6 (0.5%) (0.2%-1.1%) | 0.79 | ||||||||||||
| Fatal Bleedingc | 1 (<0.1%)b | 0 (0.0%) | -- | 0 (0.0%) | 0 (0.0%) | -- | ||||||||||||
Bleeding into a critical organ n (%) | 1 (<0.1%) | 0 (0.0%) | -- | 1 (0.1%) | 2 (0.2%) | -- | ||||||||||||
Bleeding leading to reoperation n (%) | 2 (0.1%) | 1 (<0.1%) | -- | 5 (0.4%) | 4 (0.3%) | -- | ||||||||||||
Clinically overt extra-surgical site bleeding leading to a fall in hemoglobin n (%) | 2 (0.1%) | 1 (<0.1%) | -- | 1 (0.1%) | 0 (0.0%) | -- | ||||||||||||
Clinically overt extra-surgical site bleeding leading to transfusion of ≥2 units of blood n (%) | 2 (0.1%) | 1 (<0.1%) | -- | 1 (0.1%) | 0 (0.0%) | -- | ||||||||||||
| RECORD 1 (THR) | RECORD 3 (TKR) | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
Rivaroxaban 10 mg od N=2209 | Enoxaparin 40 mg od N=2224 | P-Value | Rivaroxaban 10 mg od N=1220 | Enoxaparin 40 mg od N=1239 | P-Value | ||||||||||
Nonmajor Bleeding n (%) | 128 (5.8%) | 129 (5.8%) | -- | 53 (4.3%) | 54 (4.4%) | -- | |||||||||
Clinically relevant nonmajor bleeding n (%) | 65 (2.9%) | 54 (2.4%) | -- | 33 (2.7%) | 28 (2.3%) | -- | |||||||||
Hemorrhagic wound complicationse n (%) | 34 (1.5%) | 38 (1.7%) | -- | 25 (2.0%) | 24 (1.9%) | -- | |||||||||
- a Patients may have had more than one type of event, and an event could fall into more than one category; adjudicated treatment-emergent bleeding events included those beginning after the initiation of the study drug and up to 2 days after last dose of the study drug.
- b Major bleeding events included: (1) fatal, (2) bleeding into a critical organ (e.g, retroperitoneal, intracranial, intraocular, or intraspinal bleeding/hemorrhagic puncture), (3) bleeding requiring reoperation, (4) clinically overt extra-surgical site bleeding associated with ≥2 g/dL fall in hemoglobin or leading to infusion of ≥2 units of whole blood or packed cells.
- c The event occurred before the administration of the first dose of rivaroxaban.
- d Nonmajor bleeding events were bleeding events that did not fulfill the criteria of major bleeding.
- e Composite of excessive wound hematoma and reported surgical-site bleeding.
Phase III Supportive Study
RECORD 2 was a randomized, double-blind, double-dummy, prospective study conducted in 2509 randomized patients (safety population = 2457; mITT = 1733) undergoing THR. The aim of RECORD 2 was to assess extended thromboprophylaxis with rivaroxaban for 35±4 days. RECORD 2 was similar in study design, inclusion/exclusion criteria and endpoints to RECORD 1, except that enoxaparin 40 mg once daily (first dose given preoperatively) was given for a shorter duration (12±2 days) than rivaroxaban 10 mg od (35±4 days). Comparative efficacy claims to enoxaparin may not be drawn from this study, due to the differences in the treatment duration of rivaroxaban and enoxaparin.
Table 20 - RECORD 2 (THR): Superiority Analysis for Total VTE (Primary Composite Endpoint)a, Major VTE (Main Secondary Endpoint)b and Their Components, and Other Selected Efficacy Endpoints – Modified ITTc (MITT) Population Through the Double-Blind Treatment Period
| Parameter | Rivaroxaban 10 mg od for 35±4 days | Enoxaparin 40 mg for 12±2 days | Absolute Risk Reduction | P-Value | Relative Risk Reduction | P-Value | ||
|---|---|---|---|---|---|---|---|---|
| n/N | % (95% CI) | n/N | % (95% CI) | % (95% CI) | % (95% CI) | |||
| Total VTE | 17/864 | 2.0% (1.2% to 3.1%) | 81/869 | 9.3% (7.5% to 11.5%) | 7.3% (5.2% to 9.4%) | <0.0001 | 79% (65% to 87%) | < 0.001 |
| Major VTE | 6/961 | 0.6% (0.2% to 1.4%) | 49/962 | 5.1% (3.8% to 6.7%) | 4.5% (3.0% to 6.0%) | <0.0001 | 88% (71% to 95%) | < 0.001 |
| Death from all causes | 2/864 | 0.2% (<0.1% to 0.8%) | 6/869 | 0.7% (0.3% to 1.5%) | 0.5% (-0.2% to 1.3%) | 0.29 | -- | -- |
| Nonfatal PE | 1/864 | 0.1% (<0.1% to 0.6%) | 4/869 | 0.5% (0.1% to 1.2%) | 0.3% (-0.2% to 1.1%) | 0.37 | -- | -- |
| DVT (proximal and/or distal) | 14/864 | 1.6% (0.9% to 2.7%) | 71/869 | 8.2% (6.4% to 10.2%) | 6.5% (4.5% to 8.5%) | <0.0001 | -- | -- |
| Proximal DVT | 5/864 | 0.6% (0.2% to 1.3%) | 44/869 | 5.1% (3.7% to 6.7%) | 4.5% (2.9% to 6.0%) | <0.0001 | -- | -- |
| Distal DVT only | 9/864 | 1.0% (0.5% to 2.0%) | 27/869 | 3.1% (2.1% to 4.5%) | 2.0% (0.7% to 3.3%) | 0.0025 | -- | -- |
| VTE-related death | 0/864 | 0% | 1/869 | 0.1% | -- | -- | -- | -- |
| Symptomatic VTEc | 3/1212 | 0.2% (<0.1% to 0.7%) | 15/120 7 | 1.2% (0.7% to 2.0%) | 1.0% (0.3% to 1.8%) | 0.0040 | -- | -- |
a Total VTE = composite of DVT (proximal and/or distal), nonfatal PE, or death from all causes.
b Major VTE = composite of proximal DVT, nonfatal PE, or VTE-related death
- c MITT = subject valid for safety analysis, has undergone appropriate surgery, has adequate assessment of thromboembolism
- d Mantel-Haenszel Weighted Reduction to Enoxaparin given for all endpoints except nonfatal PE and death from all causes, for which unweighted (exact) estimates were given. Superiority was shown if the lower limit of the CI was above zero.
- e
Safety population for Symptomatic VTE (patients valid for safety analysis who underwent the appropriate surgery). The safety population was used because assessment of symptomatic events is possible in the greater population regardless of the availability of an adequate venographic assessment.
Table 21 - RECORD 2 (THR): Detailed Overview of Treatment-Emergent Bleeding Events (Safety Population)a
Rivaroxaban 10 mg od for 35±4 days N=1228 | Enoxaparin 40 mg od for 12±2 days N=1229 | P-Value | |
|---|---|---|---|
Any Bleeding n (%)(95% CI) | 81 (6.6%) (5.3% to 8.1%) | 68 (5.5%) (4.3% to 7.0%) | 0.27 |
Major Bleedingb n (%)(95% CI) | 1 (0.1%) (0.0–0.5) | 1 (0.1%) (0.0–0.5) | 1.00 |
| Fatal bleeding | 0 (0.0%) | 0 (0.0%) | -- |
Bleeding into a critical organ n (%) | 0 (0.0%) | 1 (0.1%) | -- |
Bleeding leading to reoperation n (%) | 0 (0.0%) | 0 (0.0%) | -- |
Clinically overt extra-surgical site bleeding leading to a fall in hemoglobin n (%) | 1 (0.1%) | 0 (0.0%) | -- |
Clinically overt extra-surgical site bleeding leading to transfusion of ≥2 units of blood n (%) | 1 (0.1%) | 0 (0.0%) | -- |
Nonmajor Bleedingc n (%) | 80 (6.5%) | 67 (5.5%) | -- |
Clinically relevant nonmajor bleeding n (%) | 40 (3.3%) | 33 (2.7%) | -- |
Hemorrhagic wound complicationsd n (%) | 20 (1.6%) | 21 (1.7%) | -- |
- a Patients may have had more than one type of event, and an event could fall into more than one category; adjudicated treatment-emergent bleeding events included those beginning after the initiation of the study drug and up to 2 days after last dose of the study drug.
- b
Major bleeding events included: (1) fatal, (2) bleeding into a critical organ (e.g, retroperitoneal, intracranial, intraocular, or intraspinal bleeding/hemorrhagic puncture), (3) bleeding requiring reoperation, (4) clinically overt extra-surgical site bleeding associated with ≥2 g/dL fall in hemoglobin or leading to infusion of
≥2 units of whole blood or packed cells.
c Nonmajor bleeding events were bleeding events that did not fulfill the criteria of major bleeding.
d Composite of excessive wound hematoma and reported surgical-site bleeding.
The results from this study demonstrate that extended duration prophylaxis with 10 mg rivaroxaban od for 35 days provided clinically meaningful decreases in Total VTE, Major VTE, and symptomatic VTE in THR patients without an increased risk of bleeding.
Treatment of VTE and prevention of recurrent DVT and PE
Table 22 - Summary of the Pivotal Studies for the Treatment of VTE and Prevention of Recurrent DVT and PE
| Study | Study Design | Treatment Regimen | Patient Population |
|---|---|---|---|
| EINSTEIN DVT | multicenter, randomized, open-label, event-driven non-inferiority study for efficacy | Randomized 3449 (1731 rivaroxaban, 1718 Enox/VKA) Safety Population 3429 (1718 rivaroxaban, 1711 Enox/VKA) Per Protocol 3096 (1525 rivaroxaban, 1571 Enox/VKA) | |
Rivaroxaban 15 mg bid for 3 weeks followed by 20 mg od 3, 6 or 12 monthsa Standard Therapy Enoxaparin bid bridging to therapeutic VKA 3, 6 or 12 monthsa | |||
| EINSTEIN PE | Randomized 4833, (2420 rivaroxaban, 2413 Enox/VKA) Safety Population 4817 (2412 rivaroxaban, 2405 Enox/VKA) Per Protocol 4462 (2224 rivaroxaban, 2238 Enox/VKA) | ||
EINSTEIN Extension | multicenter, randomized, double-blind, placebo-controlled, event- driven, superiority study for efficacy in subjects with symptomatic proximal DVT or PE | Rivaroxaban 20 mg once daily or placebo for 6 or 12 monthsa | Randomized 1197 (602 rivaroxaban, 594 placebo) |
| EINSTEIN CHOICE | Rivaroxaban 10 mg, or 20 mg or ASA 100 mg once dailyb | Randomized 3396 (1121 rivaroxaban 20 mg, 1136 rivaroxaban 10 mg, 1139 ASA 100 mg) | |
- a Treatment duration as determined by investigator
- b
Individual (actual) treatment duration depends on the individual randomization date: either 12 months, 9 to <12 months or 6 months
Safety population = The safety population comprised those subjects who received at least one dose of study medication.
bid = twice daily; od = once daily; VKA = vitamin K antagonist; enox = enoxaparin; ASA= acetylsalicylic acid
The EINSTEIN clinical development program consisted of four Phase III studies. The EINSTEIN DVT and EINSTEIN PE studies evaluated the treatment of VTE and prevention of recurrent DVT and PE. The EINSTEIN Extension study evaluated the benefit of continued treatment in subjects for whom clinical uncertainty regarding the absolute risk-benefit of extended duration existed.
Patients with VTE who were treated either with rivaroxaban or enoxaparin/VKA for 6 or 12 months in
EINSTEIN DVT or EINSTEIN PE, or who were treated for 6 to 14 months with VKA and in whom there was equipoise to continue anticoagulant treatment were eligible for enrollment into EINSTEIN Extension. Subjects considered to have been adequately treated with 6 to 12 months of therapy or those who required more prolonged anticoagulation therapy were not included.
In EINSTEIN CHOICE, patients with confirmed symptomatic VTE who completed 6-12 months of anticoagulant treatment and in whom there was equipoise to continue anticoagulant treatment were eligible for the study. Patients with an indication for continued therapeutic-dosed anticoagulation were excluded.
Duration of administration in EINSTEIN DVT was up to 12 months (i.e., 3, 6 or 12 months) as determined by the investigator, prior to randomization, based on local risk assessment and guidelines. Nearly half of the subjects were treated for 6 to 9 months.
In EINSTEIN DVT, and EINSTEIN PE rivaroxaban was compared to the standard dual-drug regimen of enoxaparin administered for at least 5 days in combination with VKA until the PT/INR was in therapeutic range (≥ 2.0). VKA alone was then continued, dose-adjusted to maintain the PT/INR values within the therapeutic range of 2.0 to 3.0.
Table 23 - Co-morbid Diseases and Characteristics of Patients in EINSTEIN DVT, EINSTEIN PE and EINSTEIN Extension – ITT Population
| EINSTEIN DVT | EINSTEIN PE | EINSTEIN Extension | EINSTEIN CHOICE | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Males (%) | 57% | 53% | 58% | 55% | ||||||||
| Age, mean (years) | 56 | 58 | 58 | 59 | ||||||||
| Creatinine Clearance (mL/min) | ||||||||||||
| < 50 | 7% | 8% | 7% | 5% | ||||||||
| 50 to < 80 | 23% | 25% | 21% | 25% | ||||||||
| ≥ 80 | 68% | 66% | 62% | 70% | ||||||||
| Risk Factors | ||||||||||||
| Patients with idiopathic DVT/PE | 48% | 49% | 59% | 41% | ||||||||
| Recent surgery or trauma | 19% | 17% | 4.1% | 13% | ||||||||
| Immobilization | 15% | 16% | 14% | 11% | ||||||||
| Previous VTE | 19% | 19% | 16% | 18% | ||||||||
| Mean TTR, Enox/VKA arm | 58%a | 63%b | n/a | n/a | ||||||||
| North American subjects | 64% | 63% | n/a | n/a | ||||||||
| Pre-randomization anticoagulationc | 73% | 92% | n/a | n/a | ||||||||
| Actual Treatment Duration in rivaroxaban arm | ||||||||||||
| ≥ 3 months | 92% | 92% | 91% | n/a | ||||||||
| ≥ 6 months | 68% | 73% | 62% | n/a | ||||||||
| ≥ 12 months | 3% | 4% | 2% | n/a | ||||||||
a Unadjusted Mean TTR. Adjusted Mean TTR is 60%.
b Adjusted mean TTR.
c Pre-randomization anticoagulation was limited to 24 hours in the majority of cases.
n/a=not applicable
Table 24 - Efficacy outcomes in EINSTEIN DVT, EINSTEIN PE and EINSTEIN Extension – ITT population
| EINSTEIN DVT | EINSTEIN PE | EINSTEIN Extension | |||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Rivaroxaban N=1731 | Enox/VKA N=1718 | HRa (95% CI) P-value | Rivaroxaban N=2419 | Enox/VKA N=2413 | HRa (95% CI) P-value | Rivaroxaban N=602 | Placebo N=594 | HRb (95% CI) P-value | |||||||||||||||||||||||||||
| Symptomatic Recurrent VTEb | 36 (2.1%) | 51 (3.0%) | 0.68 | 50 (2.1%) | 44 (1.8%) | 1.12 | 8 (1.3%) | 42 (7.1%) | 0.18 | ||||||||||||||||||||||||||
| (0.44-1.04) | (0.754-1.68) | (0.09-0.39) | |||||||||||||||||||||||||||||||||
| P<0.001a | P=0.0026a | P<0.001 | |||||||||||||||||||||||||||||||||
| Type of Symptomatic Recurrent VTE | |||||||||||||||||||||||||||||||||||
| Fatal PE | 1 (<0.1%) | 0 | - | 3 (0.1%) | 1 | (<0.1%) | 0 | 1 (0.2%) | |||||||||||||||||||||||||||
Death where PE could not be ruled out | 3 (0.2%) | 6 (0.3%) | - | 8 (0.3%) | 6 (0.2%) | - | 1 (0.2%) | 0 | - | ||||||||||||||||||||||||||
| Recurrent PE only | 20 (1.2%) | 18 (1.0%) | - | 23 (1.0%) | 20 (0.8%) | - | 2 (0.3%) | 13 (2.2%) | - | ||||||||||||||||||||||||||
| Recurrent DVT plus PE | 1 (<0.1%) | 0 | - | 0 | 2 (<0.1%) | - | n.a. | n.a | - | ||||||||||||||||||||||||||
| Recurrent DVT only | 14 (0.8%) | 28 (1.6%) | - | 18 (0.7%) | 17 (0.7%) | - | 5 (0.8%) | 31 (5.2%) | - | ||||||||||||||||||||||||||
| Symptomatic recurrent VTE | 69 (4.0%) | 87 (5.1%) | 0.72 | 97 ( 4.0%) | 82 (3.4%) | 1.16 | 8 (1.3%) | 43 (7.2%) | 0.18 | ||||||||||||||||||||||||||
| and all-cause mortality | (0.53-0.99) | (0.86-1.55) | (0.085-0.38) | ||||||||||||||||||||||||||||||||
| P =0.044c | P =0.3333c | (P<0.0001)c | |||||||||||||||||||||||||||||||||
| Net Clinical Benefit | 51 (2.9%) | 73 (4.2%) | 0.67 | 83 (3.4%) | 96 (4.0%) | 0.85 | 12 (2.0%) | 42 (7.1%) | 0.28 | ||||||||||||||||||||||||||
| (0.47-0.95) | (0.63-1.14) | (0.15-0.53) | |||||||||||||||||||||||||||||||||
| P =0.027c | P =0.2752c | P<0.0001 | |||||||||||||||||||||||||||||||||
| All On-Treatment Vascular | 12 (0.7%) | 14 (0.8%) | 0.79 | 35 (1.5%) | 37 (1.5%) | 0.94 | 3 (0.5) | 44 (0.7%) | 0.74 | ||||||||||||||||||||||||||
| Events | (0.36–1.71) | 0.59-1.49 | (0.17-3.3) | ||||||||||||||||||||||||||||||||
| P=0.55c | P=0.7780)c | P =0.69 | |||||||||||||||||||||||||||||||||
| All-cause Mortality | 38 (2.2%) | 49 (2.9%) | 0.67 | 58 (2.4%) | 50 (2.1%) | 1.13 | 1 (0.2%) | 2 (0.3%) | - | ||||||||||||||||||||||||||
| (0.44–1.02) | (0.77-1.65) | ||||||||||||||||||||||||||||||||||
| (P=0.06)c | P=0.5260 | ||||||||||||||||||||||||||||||||||
a P-value for non-inferiority (one-sided);
b Some patients had more than one event
c P-value for superiority (two-sided)
n.a.=not assessed
Table 25 - Efficacy outcomes in EINSTEIN CHOICE
Rivaroxaban 10 mg N=1127 | Rivaroxaban 20 mg N=1107 | ASA 100 mg N=1131 | Rivaroxaban 20 mg vs. ASA 100 mg HRa (95% CI) P-value | Rivaroxaban 10 mg vs. ASA 100 mg HRa (95% CI) P-value | |
|---|---|---|---|---|---|
| Symptomatic Recurrent VTEb | 13 (1.2%) | 17 (1.5%) | 50 (4.4%) | 0.34 | 0.26 |
| (0.20-0.59) | (0.14-0.47) | ||||
| P = 0.0001c | P <0.001c | ||||
| Symptomatic recurrent VTE | 15 (1.3%) | 23 (2.1%) | 55 (4.9%) | 0.42 (0.26-0.68) | 0.27 (0.15-0.47) |
| and all-cause mortality | P=0.0005 | P<0.0001 | |||
| Net Clinical Benefit | 17 (1.5%) | 23 (2.1%) | 53 (4.7%) | 0.44 | 0.32 |
| (0.27-0.71) | (0.18-0.55) | ||||
| P = 0.0009c | P = <0.0001c |
a P-value for non-inferiority (one-sided);
b Some patients had more than one event
c P-value for superiority (two-sided)
FAS =Full Analysis SET
EINSTEIN DVT
EINSTEIN DVT met its principal objective demonstrating that rivaroxaban was non-inferior to enoxaparin/VKA for the primary outcome of symptomatic recurrent VTE (HR of 0.68 [95% CI = 0.44-1.04], P<0.001) (Table 24 and Figure 3). The results of per-protocol analyses were similar to those of the intention-to-treat analysis. The pre-specified test for superiority was not statistically significant (P = 0.0764). The incidence rates for the principal safety outcome (major or clinically relevant non-major bleeding events), as well as the secondary safety outcome (major bleeding events), were similar for both groups (HR of 0.97 [95% CI = 0.76-1.22], P = 0.77 and HR of 0.65 [95% CI = 0.33-1.30], P = 0.21, respectively). The pre-defined secondary outcome of net clinical benefit, (the composite of the primary efficacy outcome and major bleeding events), was reported with a HR of 0.67 ([95% CI = 0.47-0.95], nominal P = 0.03) in favour of rivaroxaban. The relative efficacy and safety findings were consistent regardless of pre-treatment (none, LMWH, unfractionated heparin or fondaparinux) as well as among the 3, 6 and 12-month durations. In terms of other secondary outcomes, vascular events during study treatment occurred in 12 patients (0.7%) in the rivaroxaban arm and 14 patients (0.8%) in the enoxaparin/VKA group (HR of 0.79 [95% CI = 0.36-1.71], P = 0.55), and total mortality accounted for 38 (2.2%) vs. 49 (2.9%) patients in the rivaroxaban vs. enoxaparin/VKA arms, respectively, within intended treatment duration (P = 0.06).
| Figure 3: Kaplan-Meier Cumulative Event Rates for the Primary Efficacy Outcome in EINSTEIN-DVT – Intention-to-Treat Population |
|---|
EINSTEIN PE
EINSTEIN PE met its principal objective demonstrating that rivaroxaban was non-inferior to enoxaparin/VKA for the primary efficacy outcome of symptomatic recurrent VTE (HR of 1.12 [95% CI: 0.75-1.68], P=0.0026) (Table 24 and Figure 4). The results of per-protocol analyses were similar to those of the intention-to-treat analysis. The pre-specified test for superiority was not statistically significant (P =0.5737). The incidence rate of the principal safety outcome (major or clinically relevant non-major bleeding events) was similar for both groups (HR of 0.90 [95% CI: 0.76 to 1.07] P=0.2305). For major
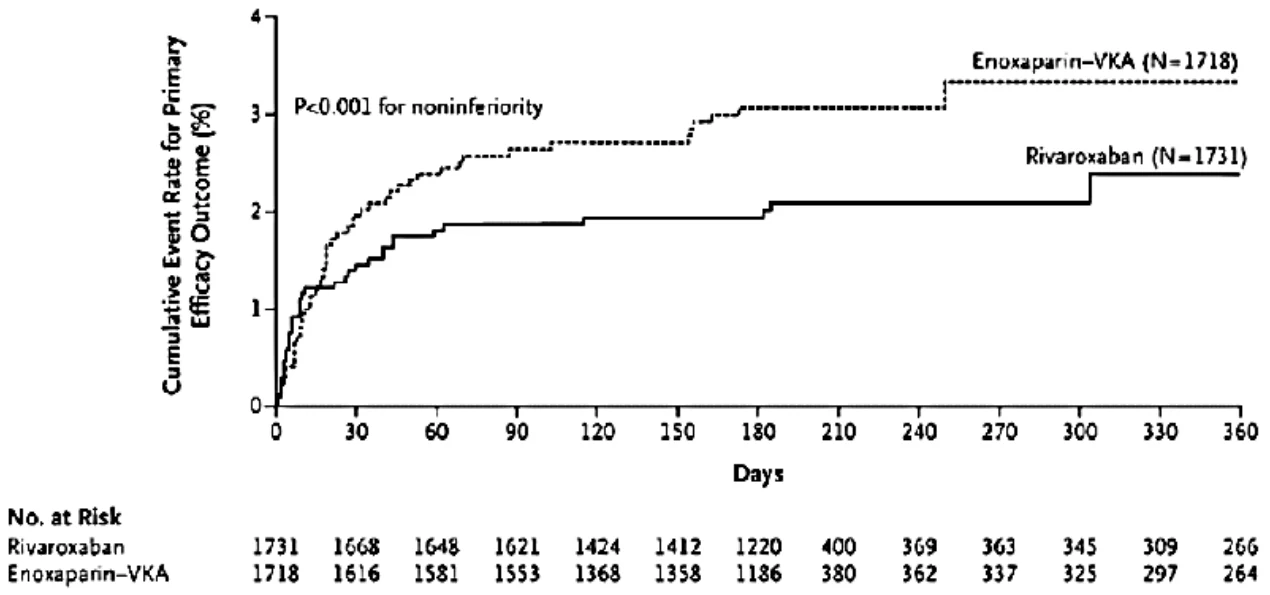 |
|---|
bleeding events, the incidence rate was nominally lower in favour of rivaroxaban treatment group (HR of 0.49 [95% CI: 0.31 – 0.79]; P=0.003). The pre-defined secondary outcome of net clinical benefit (the composite of the primary efficacy outcome and major bleeding events) was reported with a HR of 0.85 ([95% CI: 0.63-1.14]; P=0.27) in favour of rivaroxaban. The relative efficacy and safety findings were consistent regardless of pre-treatment (none, LMWH, unfractionated heparin or fondaparinux) as well as among the 3, 6 and 12 month durations. In terms of other secondary outcomes, vascular events during study treatment occurred in 41 patients (1.7%) in the rivaroxaban arm and 39 patients (1.6%) in the enoxaparin/VKA group (HR of 1.04 [95% CI = 0.67- 1.61], P = 0.86), and total mortality accounted for 58 (2.4%) vs. 50 (2.1%) patients in the rivaroxaban vs. enoxaparin/VKA arms, respectively, within intended treatment duration (P = 0.53).
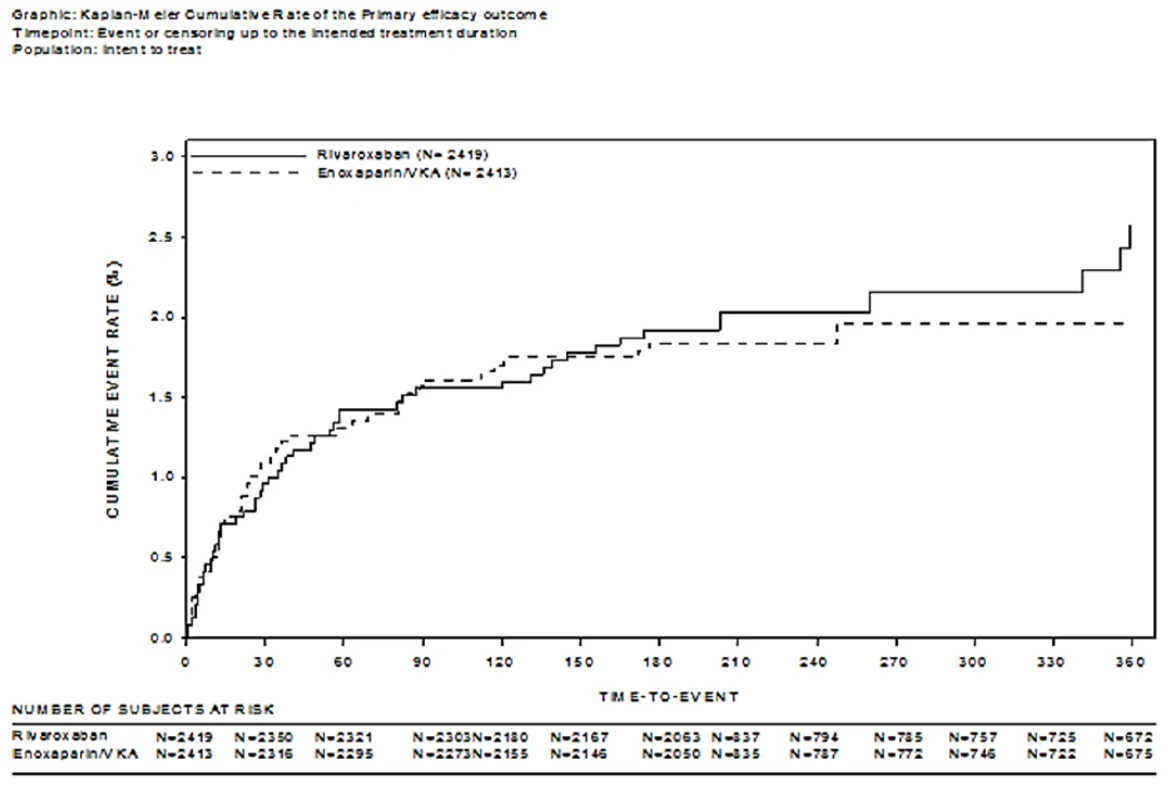
Figure 4: Kaplan-Meier analysis: cumulative rate of primary efficacy outcome in study 11702 PE - ITT Population
EINSTEIN Extension
In the EINSTEIN Extension study, rivaroxaban was superior to placebo for the primary efficacy outcome with a HR of 0.18 [95% CI = 0.09-0.39], P<0.001 (i.e., a relative risk reduction of 82%) (Table 24 and Figure 5). For the principal safety outcome (major bleeding events) there was no significant difference between patients treated with rivaroxaban compared to placebo (P = 0.11). The pre-defined secondary outcome of net clinical benefit, defined as the composite of the primary efficacy outcome and major bleeding events, was reported with a HR of 0.28 ([95% CI = 0.15-0.53], P < 0.001) in favour of rivaroxaban. In terms of other secondary outcomes, vascular events occurred in 3 patients in the rivaroxaban arm and 4 patients in the placebo group (HR of 0.74 [95% CI = 0.17-3.3], P = 0.69), and total mortality accounted for 1 (0.2%) vs. 2 (0.3%) of patients in the rivaroxaban vs. placebo arms, respectively.
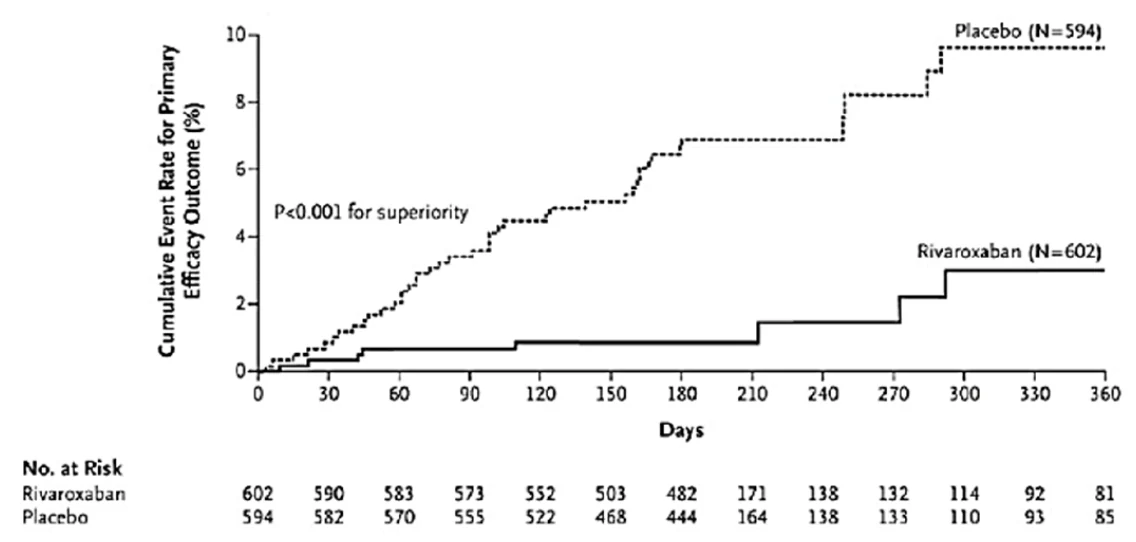
Figure 5: Kaplan-Meier Cumulative Event Rates for the Primary Efficacy Outcome in EINSTEIN Extension
EINSTEIN CHOICE
In EINSTEIN CHOICE 3,396 patients with confirmed symptomatic DVT and/or PE who completed 6-12 months of therapeutic-dose anticoagulation and who did not have an indication for continued anticoagulation in therapeutic doses, were studied for the prevention of fatal PE or non-fatal symptomatic recurrent DVT/PE. Patients with an indication for continued therapeutic- dosed anticoagulation were excluded from the study. The treatment duration was up to 12 months depending on the individual randomization date (median: 351 days). Rivaroxaban 20 mg once daily and rivaroxaban 10 mg once daily were compared with 100 mg acetylsalicylic acid once daily.
The primary efficacy outcome was symptomatic recurrent VTE defined as the composite of recurrent DVT or fatal or non-fatal PE. The secondary efficacy outcome was the composite of the primary efficacy outcome, MI, ischemic stroke, or non-CNS systemic embolism.
In the EINSTEIN CHOICE study, the primary efficacy objective for superiority was met for both rivaroxaban 20 mg and 10 mg versus acetylsalicylic acid 100mg. The secondary efficacy outcome was significantly reduced when comparing rivaroxaban 20 mg or 10 mg vs. 100 mg acetylsalicylic acid. The principal safety outcome (major bleeding events) was similar for patients treated with rivaroxaban 20 mg and 10 mg once daily compared to 100 mg acetylsalicylic acid. The secondary safety outcome (non-major bleeding associated with treatment cessation of more than 14 days) was similar when comparing rivaroxaban 20 mg or 10 mg vs. 100 mg acetylsalicylic acid. Outcomes were consistent across the patients with provoked and unprovoked VTE (see Table 25).
In a prespecified net clinical benefit analysis (NCB) (primary efficacy outcome plus major bleeding events) of EINSTEIN CHOICE, a HR of 0.44 (95% CI 0.27 - 0.71, p = 0.0009) for rivaroxaban 20 mg once daily vs 100 mg acetylsalicylic acid once daily and a HR of 0.32 (95% CI 0.18 - 0.55, p <0.0001) for rivaroxaban 10 mg once daily vs 100 mg acetylsalicylic acid once daily were reported.
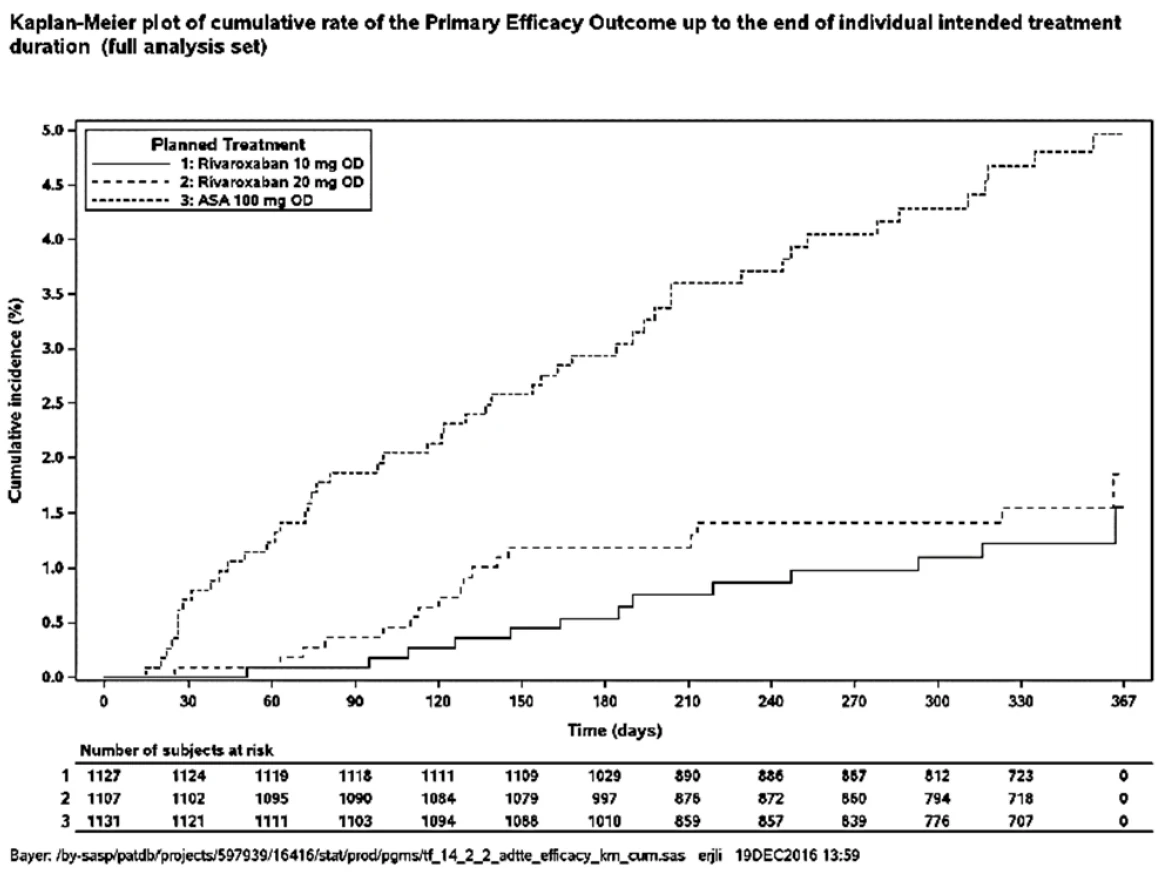
Figure 6: Kaplan-Meier analysis: cumulative event rates of the primary efficacy outcome until the end of individual intended treatment duration (FAS)
PHASE IV STUDIES
Phase IV clinical studies (XALIA) were done to evaluate the effects of rivaroxaban use under real-world (clinical practice) conditions.
XALIA
In addition to the Phase III EINSTEIN program, a prospective, non-interventional, open-label cohort study (XALIA) investigated the long-term safety of rivaroxaban under real-world conditions (central outcome adjudication including recurrent VTE, major bleeding and death. In 2619 rivaroxaban-treated patients, rates of major bleeding, recurrent VTE and all-cause mortality for rivaroxaban were 0.7%, 1.4% and 0.5%, respectively.
These results are consistent with the established safety profile of rivaroxaban in this population.
Prevention of Stroke and Systemic Embolism in Patients with Atrial Fibrillation
Table 26 - Summary of the ROCKET AF Trial, a Phase III Clinical Trial in Atrial Fibrillation
| Study | Study Design | Treatment Regimen | Populations |
|---|---|---|---|
| ROCKET AF | Rivaroxaban 20 mg od (15 mg od for patients with moderate renal impairment [CrCl 30 – 49 mL/min]) Warfarin dose adjusted to an INR of 2.5 (range 2.0 to 3.0) | Randomized 14,264 (7131 rivaroxaban, 7133 warfarin) Safety Population 14,236 (7111 rivaroxaban, 7125 warfarin) Per Protocol 14,054 (7008 rivaroxaban, 7046 warfarin) |
Randomized = The randomized / intent-to-treat population represent all uniquely randomized patients.
Safety Population = The safety population comprised those patients who received at least 1 dose of study drug.
Per Protocol = The per-protocol population was all intent to-treat patients excluding those who have specific pre-defined major protocol deviations that occur by the time of enrollment into the study or during the trial.
od = once daily
Evidence for the effectiveness of rivaroxaban is derived from the ROCKET AF trial, a prospective, randomized, double-blind, double-dummy, parallel-group, multicenter, pivotal clinical study comparing the efficacy and safety of once daily oral rivaroxaban with dose-adjusted warfarin in patients with atrial fibrillation at risk of stroke or systemic embolism. In addition to documented atrial fibrillation, patients had prior stroke, TIA or systemic embolism, or 2 or more of the following risk factors without prior stroke:
- clinical heart failure and/or left ventricular ejection fraction ≤35%
- hypertension
- age ≥75 years
- diabetes mellitus
Patients with prosthetic heart valves, or those with hemodynamically significant rheumatic heart disease, especially mitral stenosis, were excluded from the ROCKET AF study, and thus were not evaluated. These trial results do not apply to patients these conditions, whether in the presence or absence of atrial fibrillation (see 7 WARNINGS AND PRECAUTIONS – Cardiovascular, Patients with valvular disease).
The primary objective of this study was to demonstrate that rivaroxaban, a direct Factor-Xa inhibitor, was non-inferior to warfarin in reducing the occurrence of the composite endpoint of stroke and systemic embolism. If non-inferiority was shown, a pre-specified step-wise multiple testing procedure was undertaken to determine whether rivaroxaban was superior to warfarin in primary and secondary endpoints.
The study design, treatment regimen and patient populations are summarized in Table 27 and Table 28. A total of 14,264 patients were randomized with a mean age of 71 years (range 25 to 97 years) and a mean CHADS2 score of 3.5. Patients were randomized to 20 mg once daily rivaroxaban (15 mg in patients with moderate renal impairment at screening) or to dose-adjusted warfarin, titrated to an INR of 2.0 to 3.0. ROCKET AF had a mean treatment duration of 572 days of rivaroxaban given as a fixed dose without routine coagulation monitoring.
ROCKET AF studied patients with significant co-morbidities, e.g., 55% secondary prevention population (prior stroke / TIA / systemic embolism), see Table 27. For patients randomized to warfarin, the time-in-therapeutic range (TTR) of 2.0 to 3.0 was a mean of 55% (cf. 64% in North American patients).
Table 27 - Co-morbid Diseases and Characteristics of Patients in ROCKET AF Trial – ITT Population
| Heart failure and/or left ventricular ejection fraction ≤35% | 62% |
|---|---|
| Hypertension | 91% |
| Age ≥ 75 years | 44% |
| Female | 40% |
| Diabetes | 40% |
| Prior Stroke / TIA / Systemic Embolism | 55% |
| Strokea | 34% |
| TIAa | 22% |
| Systemic Embolisma | 4% |
| Valvular Disease (not meeting exclusion criteria)b | 14% |
| Mean CHADS2 | 3.5 |
| Prior VKA Use | 62% |
| Prior MI | 17% |
ITT Population = 14, 264 patients | |
At baseline, 36.5% of patients were on chronic ASA, 2.4% on anticoagulants other than VKAs, 8.7% on Class III antiarrhythmics, 54.5% on angiotensin converting enzyme (ACE) inhibitors, 22.7% on angiotensin receptor blockers, 60.0% on diuretics, 24.0% on oral antidiabetics, and 65.5% on beta blockers.
ROCKET AF demonstrated that in patients with atrial fibrillation, rivaroxaban is non-inferior to warfarin in the primary efficacy endpoint, a composite of prevention of stroke and systemic embolism in the per protocol population, on-treatment analysis (rivaroxaban: 1.71%/year, warfarin 2.16%/year, HR 0.79, 95% CI 0.66-0.96, P < 0.001). As non-inferiority was met, rivaroxaban was tested, as per the pre-specified analysis, for superiority in primary and secondary endpoints. rivaroxaban demonstrated superiority over warfarin for stroke and systemic embolism in the safety population, on-treatment analysis (HR 0.79, 95% CI 0.65 to 0.95, P = 0.015), see Table 28 and Figure 7 below.
Table 28 - ROCKET AF – Time to the First Occurrence of Total Stroke and Systemic Embolism, While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Parameter | Rivaroxaban (N=7061) | Warfarin (N=7082) | Rivaroxaban vs Warfarin | |||
|---|---|---|---|---|---|---|
| n | %/year | n | %/year | Hazard Ratio (95% CI) | P-value for superiority | |
| Total stroke and systemic embolism (Primary Efficacy Outcome) | 189 | 1.70 | 243 | 2.15 | 0.79 (0.65,0.95) | 0.015* |
| Total Stroke | 184 | 1.65 | 221 | 1.96 | 0.85 (0.70,1.03) | 0.092 |
| Hemorrhagic Stroke | 29 | 0.26 | 50 | 0.44 | 0.59 (0.37,0.93) | 0.024* |
| Ischemic Stroke | 149 | 1.34 | 161 | 1.42 | 0.94 (0.75,1.17) | 0.581 |
| Unknown Stroke Type | 7 | 0.06 | 11 | 0.10 | 0.65 (0.25,1.67) | 0.366 |
| Systemic Embolism | 5 | 0.04 | 22 | 0.19 | 0.23 (0.09,0.61) | 0.003* |
| Other Endpoints | ||||||
| All Cause Death | 208 | 1.87 | 250 | 2.21 | 0.85 (0.70,1.02) | 0.073 |
| Vascular Death | 170 | 1.53 | 193 | 1.71 | 0.89 (0.73,1.10) | 0.289 |
| Myocardial Infarction | 101 | 0.91 | 126 | 1.12 | 0.81 (0.63,1.06) | 0.121 |
Safety population on-treatment analysis = Events (Adjudicated by CEC) While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
Hazard ratio (95% CI) and P-value from Cox proportional hazard model with treatment group as a covariate. p-value (two-sided) for superiority of rivaroxaban versus warfarin in hazard ratio
* Statistically significant
While the pre-specified primary analysis for superiority used the on-treatment data set for the safety population, an intention-to treat (ITT) analysis was also conducted. In this analysis, the primary endpoint occurred in 269 patients in the rivaroxaban group (2.1% per year) and in 306 patients in the warfarin group (2.4% per year) (hazard ratio, 0.88; 95% CI, 0.74 to 1.03; P < 0.001 for non-inferiority; P = 0.12 for superiority).
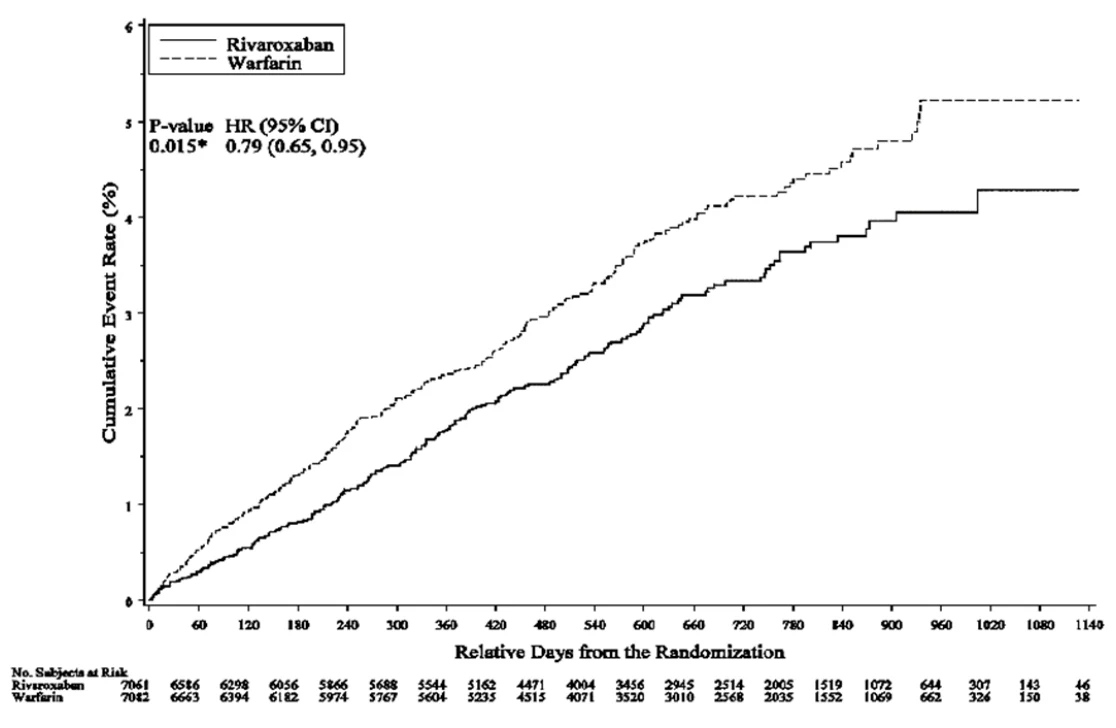
Figure 7: Kaplan-Meier curve of time to first total stroke or systemic embolism in the ROCKET AF trial safety population, on-treatment analysis, includes the 15 mg and 20 mg doses of rivaroxaban
The analysis of the principal safety endpoint demonstrates rivaroxaban has a similar rate to warfarin for the composite of major and non-major clinically relevant bleeding, see Table 29 below.
Table 29 - ROCKET AF – Time to the First Occurrence of Bleeding Events While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Parameter | Rivaroxaban (N=7111) | Warfarin (N=7125) | Rivaroxaban vs Warfarin | |||
|---|---|---|---|---|---|---|
| n | %/year | N | %/year | Hazard Ratio (95% CI) | P-value | |
| Major and Non-major clinically relevant bleeding event (Principal Safety Endpoint) | 1475 | 14.91 | 1449 | 14.52 | 1.03 (0.96,1.11) | 0.442 |
| Major Bleeding | 395 | 3.60 | 386 | 3.45 | 1.04 (0.90,1.20) | 0.576 |
| Hemoglobin Drop (2g/dL) | 305 | 2.77 | 254 | 2.26 | 1.22 (1.03,1.44) | 0.019* |
| Transfusion (> 2 units) | 183 | 1.65 | 149 | 1.32 | 1.25 (1.01,1.55) | 0.044* |
| Critical Organ Bleed | 91 | 0.82 | 133 | 1.18 | 0.69 (0.53,0.91) | 0.007* |
| Intracranial Hemorrhage | 55 | 0.49 | 84 | 0.74 | 0.67 (0.47, 0.94) | 0.019* |
| Parameter | Rivaroxaban (N=7111) | Warfarin (N=7125) | Rivaroxaban vs Warfarin | |||
|---|---|---|---|---|---|---|
| Fatal Bleed | 27 | 0.24 | 55 | 0.48 | 0.50 (0.31,0.79) | 0.003* |
| Non-major Clinically Relevant Bleeding | 1185 | 11.80 | 1151 | 11.37 | 1.04 (0.96,1.13) | 0.345 |
All analyses are based on the time to the first event. Hemoglobin drop = a fall in hemoglobin of 2 g/dL or more.
Transfusion = a transfusion of 2 or more units of packed red blood cells or whole blood.
Critical organ bleeding are cases where CEC bleeding site=intracranial, intraspinal, intraocular, pericardial, intra- articular, intramuscular with compartment syndrome or retroperitoneal.
Hazard ratio (95% CI) and P-value from Cox proportional hazard model with treatment group as a covariate. P-value (two-sided) for superiority of rivaroxaban versus Warfarin in hazard ratio.
* Statistically significant
The incidences of increased liver function tests were low and comparable between the two groups, see Table 30.
Table 30 - ROCKET AF – Incidence of Pre-specified Post-baseline Liver Function Abnormalities – Safety Population
| Parameter | Rivaroxaban (N=7111) | Warfarin (N=7125) | Rivaroxaban vs Warfarin | ||
|---|---|---|---|---|---|
| n/J | % | n/J | % | Hazard Ratio (95% CI) | |
| ALT> 3xULN | 203/6979 | 2.91 | 203/7008 | 2.90 | 1.01 (0.83,1.23) |
| ALT > 3xULN and TBL > 2xULN | 31/6980 | 0.44 | 33/7012 | 0.47 | 0.95 (0.58,1.55) |
ULN = Upper Limit of Normal Range, n = Number of patients with events, N= Number of patients valid for safety population, J = Number of patients with non-missing lab values, TBL: Total Bilirubin
Hazard Ratio (95% CI): time to event analysis using a Cox model with the treatment as the covariate.
The event rates for efficacy and safety outcomes stratified by age groups are presented in Table 31 and Table 32. The event rates for efficacy and safety outcomes stratified by renal function are presented in Table 33 and Table 34.
Table 31 - Efficacy Outcomes by Age Groups in the ROCKET AF Trial, While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/J | Event rate (%/yr) | n/J | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | ||||||||||
| Total Stroke and Systemic Embolism (Primary Efficacy Outcome) | |||||||||||||||
| All Patients | 189/7061 | 1.70 | 243/7082 | 2.15 | 0.79 (0.65,0.95) | 0.015* | |||||||||
| < 65 years | 43/1642 | 1.59 | 42/1636 | 1.53 | 1.04 (0.68,1.58) | - | |||||||||
| 65 to 75 years | 77/2767 | 1.74 | 98/2768 | 2.18 | 0.79 (0.59,1.07) | - | |||||||||
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/J | Event rate (%/yr) | n/J | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | ||||||||||||
| > 75 years | 69/2652 | 1.73 | 103/2678 | 2.54 | 0.68 (0.50,0.92) | - | |||||||||||
| > 80 years | 40/1305 | 2.17 | 46/1281 | 2.39 | 0.91 (0.60,1.40) | - | |||||||||||
| ≥85 years | 7/ 321 | 1.75 | 9/ 328 | 1.91 | 0.92 (0.34,2.47) | - | |||||||||||
| Total Stroke | |||||||||||||||||
| All Patients | 184/7061 | 1.65 | 221/7082 | 1.96 | 0.85 (0.70,1.03) | 0.092 | |||||||||||
| < 65 years | 42/1642 | 1.55 | 36/1636 | 1.31 | 1.18 (0.76,1.84) | - | |||||||||||
| 65 to 75 years | 75/2767 | 1.69 | 90/2768 | 2.00 | 0.84 (0.62,1.14) | - | |||||||||||
| > 75 years | 67/2652 | 1.68 | 95/2678 | 2.34 | 0.72 (0.52,0.98) | - | |||||||||||
| > 80 years | 38/1305 | 2.06 | 42/1281 | 2.18 | 0.95 (0.61,1.48) | - | |||||||||||
| Ischemic Stroke | |||||||||||||||||
| All Patients | 149/7061 | 1.34 | 161/7082 | 1.42 | 0.94 (0.75,1.17) | 0.581 | |||||||||||
| < 65 years | 30/1642 | 1.11 | 23/1636 | 0.84 | 1.32(0.77,2.28) | - | |||||||||||
| 65 to 75 years | 68/2767 | 1.53 | 66/2768 | 1.47 | 1.04 (0.74,1.46) | - | |||||||||||
| > 75 years | 51/2652 | 1.28 | 72/2678 | 1.77 | 0.72 (0.50,1.03) | - | |||||||||||
| > 80 years | 26/1305 | 1.41 | 33/1281 | 1.71 | 0.83 (0.50,1.39) | - | |||||||||||
| Hemorrhagic Stroke | |||||||||||||||||
| All Patients | 29/7061 | 0.26 | 50/7082 | 0.44 | 0.59 (0.37,093) | 0.024* | |||||||||||
| < 65 years | 9/1642 | 0.33 | 12/1636 | 0.44 | 0.76 (0.32,1.80) | - | |||||||||||
| 65 to 75 years | 4/2767 | 0.09 | 19/2768 | 0.42 | 0.21 (0.07,0.62) | - | |||||||||||
| > 75 years | 16/2652 | 0.40 | 19/2678 | 0.47 | 0.86 (0.44,1.67) | - | |||||||||||
| > 80 years | 12/1305 | 0.65 | 9/1281 | 0.47 | 1.40 (0.59,3.31) | - | |||||||||||
| Vascular Death | |||||||||||||||||
| All Patients | 170/7061 | 1.53 | 193/7082 | 1.71 | 0.89 (0.73,1.10) | 0.289 | |||||||||||
| < 65 years | 35/1642 | 1.29 | 44/1636 | 1.60 | 0.81 (0.52,1.26) | - | |||||||||||
| 65 to 75 years | 66/2767 | 1.49 | 70/2768 | 1.56 | 0.95 (0.68,1.33) | - | |||||||||||
| > 75 years | 69/2652 | 1.73 | 79/2678 | 1.94 | 0.89 (0.64,1.23) | - | |||||||||||
| > 80 years | 34/1305 | 1.84 | 35/1281 | 1.81 | 1.01 (0.63,1.62) | - | |||||||||||
| ≥ 85 years | 15/ 321 | 3.75 | 12/ 328 | 2.54 | 1.44 (0.67,3.08) | - | |||||||||||
Safety population on-treatment analysis = Events (Adjudicated by CEC) While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
n=number of patients with events, J=number of patients in each subgroup.
Hazard ratio (95% CI) and p-value from Cox proportional hazard model with treatment group as a covariate. P-value (two-sided) for superiority of rivaroxaban versus warfarin in hazard ratio
* Statistically significant
Table 32 - Bleeding Endpoints by Age Groups in the ROCKET AF trial, While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Rivaroxaban | Warfarin | Rivaroxaban vs. Warfarin | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/J | Event rate (%/yr) | n/J | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | ||||||||||||
| Major and Non-major Clinically Relevant Bleeding Event (Principal Safety Endpoint) | |||||||||||||||||
| All Patients | 1475/7111 | 14.91 | 1449/7125 | 14.52 | 1.03 (0.96,1.11) | 0.442 | |||||||||||
| < 65 years | 241/1646 | 9.73 | 260/1642 | 10.41 | 0.93 (0.78,1.11) | - | |||||||||||
| 65 to 75 years | 541/2777 | 13.59 | 556/2781 | 13.95 | 0.98 (0.87,1.10) | - | |||||||||||
| > 75 years | 693/2688 | 20.18 | 633/2702 | 18.09 | 1.12(1.00,1.25) | - | |||||||||||
| > 80 years | 362/1320 | 22.79 | 313/1298 | 18.84 | 1.20 (1.04,1.40) | - | |||||||||||
| ≥85 years | 89/ 326 | 25.46 | 90/ 335 | 22.29 | 1.13 (0.84,1.52) | - | |||||||||||
| Major Bleeding | |||||||||||||||||
| All Patients | 395/7111 | 3.60 | 386/7125 | 3.45 | 1.04 (0.90,1.20) | 0.576 | |||||||||||
| < 65 years | 59/1646 | 2.21 | 59/1642 | 2.16 | 1.02 (0.71,1.46) | - | |||||||||||
| 65 to 75 years | 133/2777 | 3.04 | 148/2781 | 3.34 | 0.91 (0.72,1.15) | - | |||||||||||
| > 75 years | 203/2688 | 5.16 | 179/2702 | 4.47 | 1.15 (0.94,1.41) | - | |||||||||||
| > 80 years | 118/1320 | 6.50 | 86/1298 | 4.50 | 1.44 (1.09,1.90) | - | |||||||||||
| ≥85 years | 28/ 326 | 7.05 | 32/ 335 | 6.91 | 1.01 (0.61,1.67) | - | |||||||||||
| Intracranial Hemorrhage | |||||||||||||||||
| All Patients | 55/7111 | 0.49 | 84/7125 | 0.74 | 0.67 (0.47,0.93) | 0.019* | |||||||||||
| < 65 years | 13/1646 | 0.48 | 17/1642 | 0.62 | 0.78 (0.38,1.60) | - | |||||||||||
| 65 to 75 years | 13/2777 | 0.29 | 34/2781 | 0.75 | 0.39 (0.20,0.73) | - | |||||||||||
| > 75 years | 29/2688 | 0.72 | 33/2702 | 0.81 | 0.89 (0.54,1.47) | - | |||||||||||
| > 80 years | 22/1320 | 1.18 | 15/1298 | 0.77 | 1.54 (0.80,2.96) | - | |||||||||||
| Fatal Bleeding | |||||||||||||||||
| All Patients | 27/7111 | 0.24 | 55/7125 | 0.48 | 0.50 (0.31,0.79) | 0.003* | |||||||||||
| < 65 years | 7/1646 | 0.26 | 11/1642 | 0.40 | 0.65 (0.25,1.66) | - | |||||||||||
| Rivaroxaban | Warfarin | Rivaroxaban vs. Warfarin | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/J | Event rate (%/yr) | n/J | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | ||||||||||
| 65 to 75 years | 7/2777 | 0.16 | 19/2781 | 0.42 | 0.37 (0.16,0.89) | - | |||||||||
| > 75 years | 13/2688 | 0.32 | 25/2702 | 0.61 | 0.53 (0.27,1.03) | - | |||||||||
| > 80 years | 10/1320 | 0.54 | 12/1298 | 0.62 | 0.87 (0.38,2.02) | - | |||||||||
| Non-major Clinically Relevant Bleeding | |||||||||||||||
| All Patients | 1185/7111 | 11.80 | 1151/7125 | 11.37 | 1.04 (0.96,1.13) | 0.345 | |||||||||
| < 65 years | 191/1646 | 7.62 | 210/1642 | 8.32 | 0.91 (0.75,1.11) | - | |||||||||
| 65 to 75 years | 444/2777 | 11.00 | 445/2781 | 11.02 | 1.00 (0.88,1.14) | - | |||||||||
| > 75 years | 550/2688 | 15.74 | 496/2702 | 13.93 | 1.13 (1.00,1.28) | - | |||||||||
| > 80 years | 276/1320 | 17.06 | 249/1298 | 14.74 | 1.15 (0.97,1.37) | - | |||||||||
Safety population on-treatment analysis = Events (Adjudicated by CEC) While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
n=number of patients with events, J=number of patients in each subgroup.
Hazard ratio (95% CI) and P-value from Cox proportional hazard model with treatment group as a covariate. p-value (two-sided) for superiority of rivaroxaban versus warfarin in hazard ratio
* Statistically significant
Table 33 - Efficacy Outcomes Stratified by Renal Function at Study Entry in the ROCKET AF Trial, While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/Ja | Event rate (%/yr) | n/Ja | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | |||||||||
| Total Stroke and Systemic Embolism (Primary Efficacy Outcome) | ||||||||||||||
| All Patients | 189/7061 | 1.70 | 243/7082 | 2.15 | 0.79 (0.65,0.95) | 0.015* | ||||||||
| 30 – 49 mL/min | 50/1481 | 2.36 | 60/1452 | 2.80 | 0.84 (0.58,1.22) | - | ||||||||
| 50 – 80 mL/min | 91/3290 | 1.74 | 128/3396 | 2.39 | 0.73 (0.56,0.96) | - | ||||||||
| > 80 mL/min | 47/2278 | 1.25 | 54/2221 | 1.43 | 0.87 (0.59,1.28) | - | ||||||||
| Total Stroke | ||||||||||||||
| All Patients | 184/7061 | 1.65 | 221/7082 | 1.96 | 0.85 (0.70,1.03) | 0.092 | ||||||||
| 30 – 49 mL/min | 49/1481 | 2.31 | 52/1452 | 2.42 | 0.95 (0.64,1.40) | - | ||||||||
| 50 – 80 mL/min | 88/3290 | 1.68 | 120/3396 | 2.24 | 0.75 (0.57,0.99) | - | ||||||||
| > 80 mL/min | 46/2278 | 1.22 | 48/2221 | 1.27 | 0.95 (0.64,1.43) | - | ||||||||
| Ischemic Stroke | ||||||||||||||
| All Patients | 149/7061 | 1.34 | 161/7082 | 1.42 | 0.94 (0.75,1.17) | 0.581 | ||||||||
| 30 – 49 mL/min | 43/1481 | 2.03 | 39/1452 | 1.82 | 1.11(0.72,1.72) | - | ||||||||
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | |||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/Ja | Event rate (%/yr) | n/Ja | Event rate (%/yr) | Hazard Ratio (95% CI) | P-value | ||||||||||
| 50 – 80 mL/min | 69/3290 | 1.32 | 89/3396 | 1.66 | 0.80 (0.58,1.09) | - | |||||||||
| > 80 mL/min | 36/2278 | 0.95 | 32/2221 | 0.85 | 1.12 (0.70,1.80) | - | |||||||||
| Hemorrhagic Stroke | |||||||||||||||
| All Patients | 29/7061 | 0.26 | 50/7082 | 0.44 | 0.59 (0.37,093) | 0.024* | |||||||||
| 30 – 49 mL/min | 6/1481 | 0.28 | 11/1452 | 0.51 | 0.55 (0.20,1.48) | - | |||||||||
| 50 – 80 mL/min | 15/3290 | 0.29 | 25/3396 | 0.47 | 0.62 (0.33,1.17) | - | |||||||||
| > 80 mL/min | 8/2278 | 0.21 | 14/2221 | 0.37 | 0.57 (0.24,1.35) | - | |||||||||
| Vascular Death | |||||||||||||||
| All Patients | 170/7061 | 1.53 | 193/7082 | 1.71 | 0.89 (0.73,1.10) | 0.289 | |||||||||
| 30 – 49 mL/min | 55/1481 | 2.59 | 54/1452 | 2.52 | 1.02 (0.70,1.49) | - | |||||||||
| 50 – 80 mL/min | 75/3290 | 1.43 | 91/3396 | 1.69 | 0.85 (0.62,1.15) | - | |||||||||
| > 80 mL/min | 40/2278 | 1.06 | 47/2221 | 1.24 | 0.85 (0.56,1.29) | - | |||||||||
Safety population on-treatment analysis = Events (Adjudicated by CEC) While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
n=number of patients with events, J=number of patients in each subgroup.
a= Patients with CrCl< 30 mL/min or missing baseline CrCl are excluded from the rows of CrCl subgroups (30-49 mL/min, 50-80 mL/min, >80 mL/min). The patients are, however, included in the “All Patients” rows.
Hazard ratio (95% CI) and p-value from Cox proportional hazard model with treatment group as a covariate. P-value (two-sided) for superiority of rivaroxaban versus warfarin in hazard ratio
* Statistically significant
Table 34 - Bleeding Endpoints Stratified by Renal Function at Study Entry in the ROCKET AF Trial, While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/Ja | Event rate (%/yr) | n/Ja | Event rate (%/yr) | Hazard Ratio (95% CI) | p-value | |||||||||||
| Major and Non-Major Clinically Relevant Bleeding Event (Principal Safety Endpoint) | ||||||||||||||||
| All Patients | 1475/7111 | 14.91 | 1449/7125 | 14.52 | 1.03 (0.96,1.11) | 0.442 | ||||||||||
| 30 – 49 mL/min | 336/1498 | 17.87 | 341/1472 | 18.28 | 0.98 (0.84,1.14) | - | ||||||||||
| 50 – 80 mL/min | 725/3313 | 15.74 | 719/3410 | 15.30 | 1.04 (0.93,1.15) | - | ||||||||||
| > 80 mL/min | 412/2288 | 12.15 | 388/2230 | 11.42 | 1.06(0.92,1.21) | - | ||||||||||
| Major Bleeding | ||||||||||||||||
| All Patients | 395/7111 | 3.60 | 386/7125 | 3.45 | 1.04 (0.90,1.20) | 0.576 | ||||||||||
| 30 – 49 mL/min | 99/1498 | 4.72 | 100/1472 | 4.72 | 1.00 (0.76,1.32) | - | ||||||||||
| 50 – 80 mL/min | 183/3313 | 3.54 | 197/3410 | 3.72 | 0.95 (0.78,1.17) | - | ||||||||||
| > 80 mL/min | 112/2288 | 3.02 | 89/2230 | 2.38 | 1.26 (0.95,1.67) | - | ||||||||||
| Intracranial Hemorrhage | ||||||||||||||||
| All Patients | 55/7111 | 0.49 | 84/7125 | 0.74 | 0.67 (0.47,0.93) | 0.019* | ||||||||||
| Rivaroxaban | Warfarin | Rivaroxaban vs Warfarin | ||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n/Ja | Event rate (%/yr) | n/Ja | Event rate (%/yr) | Hazard Ratio (95% CI) | p-value | |||||||||||
| 30 – 49 mL/min | 15/1498 | 0.70 | 19/1472 | 0.88 | 0.80 (0.41,1.57) | - | ||||||||||
| 50 – 80 mL/min | 27/3313 | 0.51 | 43/3410 | 0.80 | 0.64 (0.40,1.04) | - | ||||||||||
| > 80 mL/min | 13/2288 | 0.34 | 22/2230 | 0.58 | 0.59 (0.30,1.17) | - | ||||||||||
| Fatal Bleeding | ||||||||||||||||
| All Patients | 27/7111 | 0.24 | 55/7125 | 0.48 | 0.50 (0.31,0.79) | 0.003* | ||||||||||
| 30 – 49 mL/min | 6/1498 | 0.28 | 16/1472 | 0.74 | 0.38 (0.15,0.97) | - | ||||||||||
| 50 – 80 mL/min | 14/3313 | 0.27 | 24/3410 | 0.45 | 0.60 (0.31,1.16) | - | ||||||||||
| > 80 mL/min | 7/2288 | 0.19 | 15/2230 | 0.40 | 0.46 (0.19,1.14) | - | ||||||||||
| Non-major Clinically Relevant Bleeding | ||||||||||||||||
| All Patients | 1185/7111 | 11.80 | 1151/7125 | 11.37 | 1.04 (0.96,1.13) | 0.345 | ||||||||||
| 30 – 49 mL/min | 261/1498 | 13.67 | 259/1472 | 13.61 | 1.01 (0.85,1.19) | - | ||||||||||
| 50 – 80 mL/min | 596/3313 | 12.77 | 570/3410 | 11.94 | 1.08 (0.96,1.21) | - | ||||||||||
| > 80 mL/min | 327/2288 | 9.48 | 321/2230 | 9.36 | 1.01 (0.86,1.18) | - | ||||||||||
Safety population on-treatment analysis = Events (Adjudicated by CEC) While on Treatment (up to Last Dose Plus 2 Days) – Safety Population
n=number of patients with events, J=number of patients in each subgroup
a= Patients with CrCl< 30 mL/min or missing baseline CrCl are excluded from the rows of CrCl subgroups
(30-49 mL/min, 50-80 mL/min, >80 mL/min). The patients are, however, included in the “All Patients” rows.
Hazard ratio (95% CI) and p-value from Cox proportional hazard model with treatment group as a covariate. P-value (two-sided) for superiority of rivaroxaban versus warfarin in hazard ratio
* Statistically significant
PHASE IV STUDIES
Phase IV clinical studies (XANTUS) were done to evaluate the effects of rivaroxaban use under real-world (clinical practice) conditions.
XANTUS
In addition to the Phase III ROCKET AF study, a prospective, single-arm, post-authorization, non-interventional, open-label cohort study (XANTUS) with central outcome adjudication including thromboembolic events and major bleeding has been conducted. 6,704 patients with non-valvular atrial fibrillation were enrolled for prevention of stroke and non-central nervous system (CNS) systemic embolism under real-world conditions. The mean CHADS2 score of the population was 1.9. Major bleeding incidence was 2.1 per 100 patient years. Fatal hemorrhage incidence was 0.2 per 100 patient years and intracranial hemorrhage incidence was 0.4 per 100 patient years. Stroke or non-CNS systemic embolism incidence was 0.8 per 100 patient years. These results are consistent with the established safety profile of rivaroxaban in this population.
14.2 Comparative Bioavailability Studies
A randomized, two-way, single-dose, crossover comparative bioavailability study of MINT-RIVAROXABAN 10 mg tablets (Mint Pharmaceuticals Inc.) with PrXARELTO® 10 mg tablets (Bayer Inc.) was conducted in healthy, adult, Asian, male subjects under fasting conditions. Comparative bioavailability data from the 42 subjects that were included in the statistical analysis are presented in the following table:
Rivaroxaban (1 x 10 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
AUCT (ng·hr/mL) | 1718.59 1787.67 (29.27) | 1732.35 1787.83 (26.71) | 99.2 | 93.1 - 105.7 |
AUCI (ng·hr/mL) | 1761.93 1827.73 (28.12) | 1782.07 1833.43 (25.42) | 98.9 | 93.4 - 104.6 |
CMAX (ng/mL) | 184.90 199.14 (35.14) | 212.93 223.20 (31.07) | 86.8 | 76.9 - 98.0 |
TMAX3 (h) | 2.67 (0.75 - 16.00) | 2.33 (0.50 - 4.67) | ||
T½4 (h) | 6.83 (39.49) | 6.53 (41.61) | ||
1 MINT-RIVAROXABAN tablets, 10 mg (Mint Pharmaceuticals Inc.).
2 PrXARELTO® (Rivaroxaban) tablets, 10 mg (Bayer Inc., Canada).
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
A randomized, two-way, single-dose, crossover comparative bioavailability study of MINT-RIVAROXABAN 20 mg tablets (Mint Pharmaceuticals Inc.) with PrXARELTO® 20 mg tablets (Bayer Inc.) was conducted in healthy, adult, Asian, male subjects under high-fat, high-calorie fed conditions. Comparative bioavailability data from the 40 subjects that were included in the statistical analysis are presented in the following table:
Rivaroxaban (1 x 20 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | Confidence Interval |
AUCT (ng·hr/mL) | 3984.51 4150.73 (29.11) | 3893.90 4048.27 (28.23) | 102.3 | 98.6 - 106.1 |
AUCI (ng·hr/mL) | 4010.94 4178.39 (29.23) | 3921.73 4078.14 (28.28) | 102.3 | 98.6 - 106.1 |
CMAX (ng/mL) | 488.26 498.78 (20.22) | 462.21 474.91 (24.37) | 105.6 | 100.8 - 110.7 |
TMAX3 (h) | 4.33 (1.33 - 6.00) | 4.33 (1.33 - 6.00) | ||
T½4 (h) | 5.73 (23.55) | 5.68 (28.53) | ||
1 MINT-RIVAROXABAN tablets, 20 mg (Mint Pharmaceuticals Inc.).
2 PrXARELTO® (Rivaroxaban) tablets, 20 mg (Bayer Inc., Canada).
3 Expressed as the median (range) only.
4 Expressed as the arithmetic mean (CV%) only.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology (repeat-dose studies):
Rivaroxaban was tested in repeat-dose studies up to 6 months in rats and up to 12 months in dogs. Based on the pharmacological mode of action, a NOEL could not be established due to effects on clotting time. All adverse findings, except for a slight body weight gain reduction in rats and dogs, could be related to an exaggerated pharmacological mode of action of the compound. In dogs, at very high exposures, severe spontaneous bleedings were observed. The NOAELs after chronic exposure are 12.5 mg/kg in rats and 5 mg/kg in dogs.
Carcinogenicity:
In 2-year carcinogenicity studies, rivaroxaban was tested in mice, up to 60 mg/kg/day (reaching systemic exposure similar to humans) and in rats (up to 3.6-fold higher than in humans) without demonstration of carcinogenic potential.
Genotoxicity:
No genotoxicity was observed in a test for gene mutation in bacteria (Ames-Test), in an in vitro test for chromosomal aberrations, or in the in vivo micronucleus test.
Reproductive and Developmental Toxicology:
Rivaroxaban was tested in developmental toxicity studies at exposure levels of up to 38-fold (rat) and up to 89-fold (rabbit) above the therapeutic exposure in humans. The toxicological profile is mainly characterized by maternal toxicity due to exaggerated pharmacodynamic effects.
Up to the highest dose tested, no primary teratogenic potential was identified.
[14C]Rivaroxaban -related radioactivity penetrated the placental barrier in rats. In none of the fetal organs and tissues did the exposure in terms of maximum concentrations or AUC exceed the maternal blood exposure. The average exposure in the fetuses based on AUC(0-24) reached about 20% of the exposure in maternal blood. The AUC in the mammary glands was approximately equivalent to the AUC in the blood, which indicates secretion of radioactivity into milk (see 2 CONTRAINDICATIONS).
Rivaroxaban did not show an effect on male or female fertility up to 200 mg/kg.
[14C]Rivaroxaban was administered orally to lactating Wistar rats (day 8 to 10 post partum) as a single oral dose of 3 mg/kg body weight.
[14C]Rivaroxaban -related radioactivity was secreted into the milk of lactating rats only to a low extent in relation to the administered dose: The estimated amount of radioactivity excreted with milk was 2.12% of the maternal dose within 32 hours after administration (see 2 CONTRAINDICATIONS).
Juvenile Toxicity:
Rivaroxaban was tested in male and female juvenile rats up to 3-month treatment duration. Treatment started at postnatal day 4 at doses of 6, 20 and 60 mg/kg/day. Rivaroxaban was generally well tolerated except for signs indicating exaggerated pharmacodynamics (increased coagulation time). No evidence of target organ-specific toxicity or toxicity developing organs was seen.
17 SUPPORTING PRODUCT MONOGRAPHS
|
|---|