


Product Monograph - Mirena
Recent Major Label Changes
| 1 Indications | 2024-02 |
| 1 Indications, 1.2 Geriatrics | 2024-02 |
| 2 Contraindications | 2024-02 |
| 4 Dosage and Administration, 4.2 Recommended Dose and Dosage Adjustment | 2024-02 |
| 4 Dosage and Administration, 4.4 Administration | 2024-02 |
| 4 Dosage and Administration, 4.5 Missed Dose | 2024-02 |
| 7 Warnings and Precautions, Genitourinary | 2024-02 |
| 7 Warnings and Precautions, Monitoring and Laboratory Tests | 2024-02 |
| 7 Warnings and Precautions, Reproductive Health | 2024-02 |
| 7 Warnings and Precautions, 7.1.4 Geriatrics | 2024-02 |
Table of Contents
Certain sections or subsections that are not applicable at the time of the preparation of the most recent authorized product monograph are not listed.
Table of Contents ............................................................................................................................... 2
Part 1: Health Professional Information .............................................................................................. 4
1 Indications .................................................................................................................................. 4
1.1 Pediatrics ......................................................................................................................................... 4
1.2 Geriatrics ......................................................................................................................................... 4
2 Contraindications ........................................................................................................................ 4
3 Serious Warnings and Precautions Box ......................................................................................... 5
4 Dosage and Administration .......................................................................................................... 5
4.1 Dosing Considerations .................................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ............................................................................... 5
4.3 Reconstitution ................................................................................................................................. 5
4.4 Administration ............................................................................................................................... 5
4.5 Missed Dose .................................................................................................................................. 13
5 Overdose .................................................................................................................................. 13
6 Dosage Forms, Strengths, Compositions, and Packaging ............................................................. 14
7 Warnings and Precautions ........................................................................................................ 14
General ........................................................................................................................................... 14
Carcinogenesis and Mutagenesis ................................................................................................... 15
Cardiovascular ................................................................................................................................ 15
Driving and Operating Machinery .................................................................................................. 16
Endocrine and Metabolism ............................................................................................................ 16
Gastrointestinal.............................................................................................................................. 16
Genitourinary ................................................................................................................................. 16
Hematologic ................................................................................................................................... 17
Hepatic/Biliary/Pancreatic ............................................................................................................. 17
Monitoring and Laboratory Tests .................................................................................................. 17
Neurologic ...................................................................................................................................... 18
Ophthalmologic.............................................................................................................................. 18
Perioperative Considerations ........................................................................................................ 18
Psychiatric ...................................................................................................................................... 18
Reproductive Health ...................................................................................................................... 18
Sexual Function/Reproduction ...................................................................................................... 18
Skin ................................................................................................................................................. 22
7.1 Special Populations ....................................................................................................................... 22
7.1.1 Pregnancy/Intrauterine pregnancy ....................................................................................... 22
7.1.2 Breastfeeding ........................................................................................................................ 22
7.1.3 Pediatrics ............................................................................................................................... 22
7.1.4 Geriatrics .............................................................................................................................. 22
8 Adverse Reactions ..................................................................................................................... 22
8.1 Adverse Reaction Overview .......................................................................................................... 22
8.2 Clinical Trial Adverse Reactions .................................................................................................... 23
8.3 Less Common Clinical Trial Adverse Reactions ............................................................................. 24
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and other Quantitative Data .. 24
8.5 Post-Market Adverse Reactions .................................................................................................... 24
9 Drug Interactions ....................................................................................................................... 26
9.2 Drug Interactions Overview .......................................................................................................... 26
9.3 Drug-Behaviour Interactions ......................................................................................................... 26
9.4 Drug-Drug Interactions ................................................................................................................. 26
9.5 Drug-Food Interactions ................................................................................................................. 26
9.6 Drug-Herb Interactions ................................................................................................................. 26
9.7 Drug-Laboratory Test Interactions ................................................................................................ 26
10 Clinical Pharmacology .............................................................................................................. 26
10.1 Mechanism of Action .................................................................................................................. 26
10.2 Pharmacodynamics ..................................................................................................................... 27
10.3 Pharmacokinetics ........................................................................................................................ 30
11 Storage, Stability, and Disposal ................................................................................................ 32
12 Special Handling Instructions ................................................................................................... 32
Part 2: Scientific Information ............................................................................................................ 33
13 Pharmaceutical Information .................................................................................................... 33
14 Clinical Trials ........................................................................................................................... 33
14.1 Clinical Trials by Indication.......................................................................................................... 33
16 Non-Clinical Toxicology ............................................................................................................ 36
Patient Medication Information ....................................................................................................... 39
Part 1: Health Professional Information
1 Indications
MIRENA (levonorgestrel-releasing intrauterine system) is indicated for:
- conception control for maximum up to 8 years
- treatment of idiopathic menorrhagia following appropriate diagnostic investigation for up to 5 years in individuals accepting the contraceptive effect of MIRENA
1.1 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
1.2 Geriatrics
Geriatrics: MIRENA has not been studied in individuals over the age of 65 years. No data are available to Health Canada, therefore, Health Canada has not authorized an indication for geriatric use.
2 Contraindications
MIRENA (levonorgestrel-releasing intrauterine system) is contraindicated in individuals with the following conditions:
- known or suspected pregnancy
- current or recurrent pelvic inflammatory disease
- lower genital tract infection
- postpartum endometritis
- undiagnosed abnormal uterine bleeding
- uterine anomalies including fibroids if they distort the uterine cavity
- uterine or cervical malignancy
- known or suspected progestin-dependent neoplasia, including breast cancer
- cervicitis
- cervical dysplasia
- active liver disease or dysfunction
- actual benign or malignant liver tumors
- septic abortion within the previous three months
- hypersensitivity to levonorgestrel or any of the other ingredients in the formulation or components of MIRENA. For a complete listing, see the 6 Dosage Forms, Strengths, Compositions, and Packaging section of the Product Monograph.
- bacterial endocarditis
- established immunodeficiency
- acute malignancies affecting blood or leukemias
- recent trophoblastic disease while hCG levels are elevated
- a previously inserted intrauterine device (IUD) that has not been removed
- conditions associated with increased susceptibility to pelvic infections
3 Serious Warnings and Precautions Box
Hormonal contraceptives DO NOT PROTECT against Sexually Transmitted Infections (STIs)
including HIV/AIDS. For protection against STIs, it is advisable to use latex or polyurethane condoms IN COMBINATION WITH MIRENA.
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels.
Individuals should be counseled not to smoke (see 7 Warnings and Precautions - Cardiovascular section).
Uterine Perforation may occur with the use of intrauterine contraceptives including MIRENA
(see 7 Warnings and Precautions - Uterine Perforation section).
4 Dosage and Administration
4.1 Dosing Considerations
Not Applicable
4.2 Recommended Dose and Dosage Adjustment
Conception Control
Following insertion into the uterine cavity, MIRENA is effective for conception control up to 8 years. If after 8 years, continued use of MIRENA is desired, a new MIRENA system should be inserted immediately after the old one is removed.
Treatment of Idiopathic Menorrhagia
Following insertion into the uterine cavity, MIRENA is effective for treatment of idiopathic menorrhagia for up to 5 years. If after 5 years, continued use of MIRENA is desired, a new MIRENA system should be inserted immediately after the old one is removed. Data on use for this indication beyond 5 years are limited.
For estimated in vivo release rates of LNG from MIRENA for different points in time, please see 10 Clinical Pharmacology – 10.3 Pharmacokinetics.
4.3 Reconstitution
Not Applicable
4.4 Administration
Medical Examination/Consultation
Before insertion, the MIRENA user must be informed of the efficacy, risks and side effects of MIRENA. A thorough history and physical examination should also be performed prior to insertion, including a blood pressure determination. Breasts, liver, extremities, and pelvic organs should be examined. Cervical smear (Papanicolaou smear) should be performed as needed, according to healthcare professional’s evaluation. Pregnancy and sexually transmitted infections should be excluded and any genital infections must be successfully treated. For timing of insertion to exclude pregnancy see 4 Dosage and Administration– Insertion, Removal and Replacement. The position of the uterus and the size of the uterine cavity should be determined. Fundal positioning of MIRENA is particularly important in order to ensure uniform exposure of the endometrium to the progestogen, prevent expulsion and maximize efficacy. Because irregular bleeding is common during the first months of therapy, it is recommended to exclude endometrial pathology before insertion of MIRENA (see 7 Warnings and Precautions – Genitourinary: Bleeding irregularities; and 8 Adverse Reactions). It is also important to counsel individuals about how their bleeding pattern may change after insertion of MIRENA. The instructions for insertion should be followed carefully. Users of MIRENA should be re-examined 4 to 12 weeks after insertion and once a year thereafter, or more frequently if clinically indicated.
MIRENA is not suitable for use as a postcoital contraceptive.
Insertion, Removal and Replacement
In individuals of fertile age, MIRENA should be inserted within seven days of the onset of menstruation. In this case no back up contraception is needed. MIRENA can be inserted any time during the cycle if the healthcare professional can be reasonably certain (as defined by the World Health Organization) that the individual is not pregnant. If insertion is more than seven days since menstrual bleeding started, a barrier method of contraception should be used or the MIRENA user should abstain from vaginal intercourse for the next seven days to prevent pregnancy. Consider the possibility of ovulation and conception before using this product. MIRENA may be replaced by a new system at any time during the cycle. The system can also be inserted immediately after first trimester abortion.
Insertions following second trimester abortion should be postponed for a minimum of 6 weeks or until the uterus is fully involuted. If involution is delayed, wait until involution is complete before insertion.
Postpartum insertions should be postponed until the uterus is fully involuted, and not earlier than six weeks after delivery. If involution is substantially delayed, consider waiting until 12 weeks postpartum. In case of a difficult insertion and/or exceptional pain or bleeding during or after insertion, the possibility of perforation should be considered and appropriate steps should be taken, such as physical examination and ultrasound.
If bleeding irregularities develop during prolonged treatment, appropriate diagnostic measures should be undertaken.
For conception control, the system should be removed or replaced after 8 years of use.
For idiopathic menorrhagia, the system should be removed or replaced after 5 years of use. Data on use in this indication beyond 5 years are limited.
MIRENA can be removed by applying gentle traction on the threads with forceps. The use of excessive force during removal may cause damage to the system. After removal of MIRENA, verify that the system is intact.
If the threads are not visible, determine the location of MIRENA by ultrasound or other methods. If MIRENA is found in the uterine cavity, it may be removed using forceps. This may require dilatation of the cervical canal or other surgical intervention, such as hysteroscopy.
During difficult removals (i.e., removal through a tight cervical canal or surgical removal after perforation), the hormone cylinder may slide over and cover the horizontal arms. This situation generally does not require further intervention once the system is verified to be intact. The reporting rate for hormone cylinder dislocation/shifting with MIRENA is approximately 7 per 1 million insertions.
If the user wishes to continue using MIRENA, a new system can be inserted at the time of removal of the old one. If pregnancy is not desired, removal should be carried out within 7 days of the onset of menstruation in users of fertile age provided the user is experiencing regular menses.
If the system is removed at some other time or the user does not experience regular menses and has had intercourse within a week, they are at risk of pregnancy unless a new system is inserted immediately following removal. If MIRENA will not be replaced, the individual should consider starting a new contraceptive method a week prior to removal.
Insertion and removal may be associated with some pain and bleeding. The procedure may cause a fainting spell or precipitate a seizure in an epileptic individual. It is recommended to wait 24 to 48 hours before having sexual intercourse in the event of general discomfort after insertion of MIRENA.
Expulsion
For Expulsion, see 7 Warnings and Precautions – Sexual Function/Reproduction; Expulsion.
Lost Removal Threads
If the threads are not visible upon follow-up examination, they may have retracted into the uterus or broken, or MIRENA may have broken, perforated the uterus, or been expelled. If the length of the threads has changed from the length at the time of insertion, the system may have become displaced (see 7 Warnings and Precautions – Sexual Function/Reproduction; Expulsion). Pregnancy must be excluded and the location of MIRENA must be verified by sonography, X-ray (MIRENA is radiopaque), or by gentle exploration of the uterine cavity with a probe. If MIRENA is displaced, remove it. A new MIRENA may be inserted at that time or during the next menses if it is certain that conception has not occurred.
Insertion Instructions
Before insertion, the MIRENA user must be informed of the efficacy, risks and side effects of MIRENA.
Because the insertion technique is different from other intrauterine devices, it is important that health care professionals receive training on the correct insertion technique.
Health care professionals should become thoroughly familiar with the insertion instructions in their entirety before insertion of MIRENA
MIRENA is supplied in a sterile package which should not be opened until required for insertion. MIRENA is sterilized with ethylene oxide. Do not resterilize. MIRENA is for single use only. Do not use if the seal of the sterile package is broken, or if the package is damaged or opened. The exposed product should be handled with aseptic precautions. Insert MIRENA before the expiry date indicated on the label.
MIRENA is supplied with Insertion Instructions, as well as a reminder card in the outer package. Complete the reminder card and give it to the MIRENA user after insertion.
In individuals of fertile age, MIRENA is inserted into the uterine cavity using the enclosed inserter within seven days of the onset of menstruation by carefully following these insertion instructions (Figure 1). In this case no back up contraception is needed. MIRENA can be inserted any time during the cycle if the healthcare professional can be reasonably certain (as defined by the World Health Organization) that the individual is not pregnant. If insertion is more than seven days since menstrual bleeding started, a barrier method of contraception should be used or the MIRENA user should abstain from vaginal intercourse for the next seven days to prevent pregnancy. Consider the possibility of ovulation and conception before using this product. MIRENA is not suitable for use as postcoital contraceptive. It can be replaced by a new system at any time during the menstrual cycle. For additional information on the timing of insertion, please see the 4 Dosage and Administration - 4.4 Administration; Insertion, Removal and Replacement subsection of the Product Monograph.
A physical examination including pelvic examination, examination of the breasts and cervical smear should be performed prior to insertion. Conduct a gynecological examination of the individual to establish the size and position of the uterus and to exclude pregnancy or other genital tract contraindications for the use of MIRENA.
Preparation for Insertion
Visualize the cervix with the aid of a speculum and thoroughly cleanse the cervix and vagina with a suitable antiseptic solution.
Grasp the upper lip of the cervix with a tenaculum or suitable holding forceps to stabilize the uterus. If the uterus is retroverted, it may be more appropriate to grasp the lower lip of the cervix. Gentle traction on the holding forceps can be applied to straighten the cervical canal. The forceps should remain in position and gentle traction on the cervix should be maintained throughout the insertion procedure.
Gently advance a uterine sound through the cervical canal to the fundus to determine the depth and confirm the direction of the uterine cavity, and to exclude any evidence of intrauterine abnormalities (e.g., uterine septum, synechiae or submucosal fibroids) or a previously inserted intrauterine contraceptive which has not been removed. If difficulty is encountered, consider dilatation of the canal. If cervical dilatation is required, consider using analgesics and/or paracervical block.
Insertion
Step 1–Opening of the sterile package
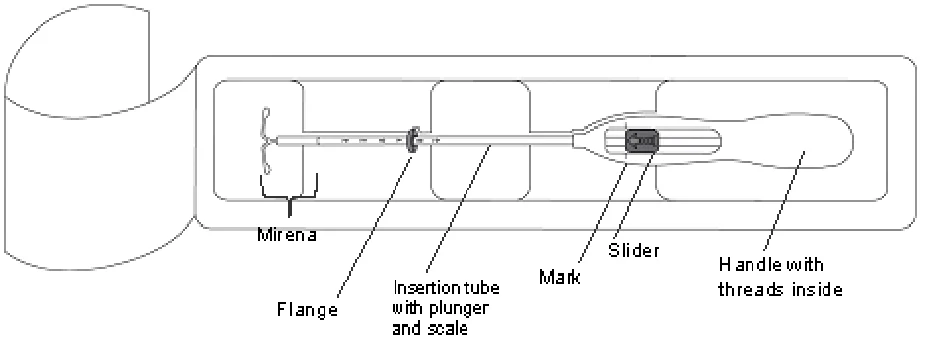
First, open the sterile package completely (Figure 1). Then use aseptic technique and sterile gloves.
Figure 1: Sterile Package Containing MIRENA
Step 2–Load MIRENA into the insertion tube
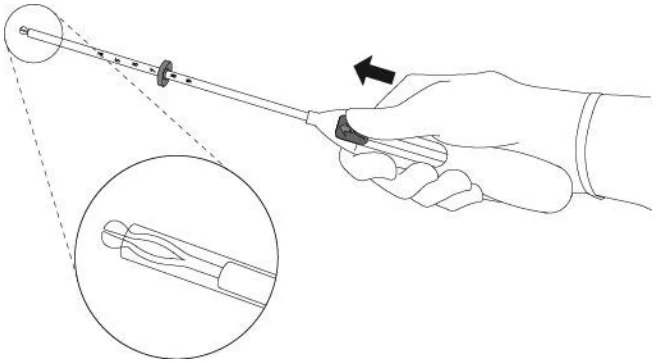
- To load MIRENA into the insertion tube, push the slider forward in the direction of the arrow to the furthest position (Figure 2).
IMPORTANT! Do not pull the slider downwards as this may prematurely release MIRENA. Once released, MIRENA cannot be re-loaded.
Figure 2: Loading MIRENA into the Insertion Tube
Step 3–Setting the flange
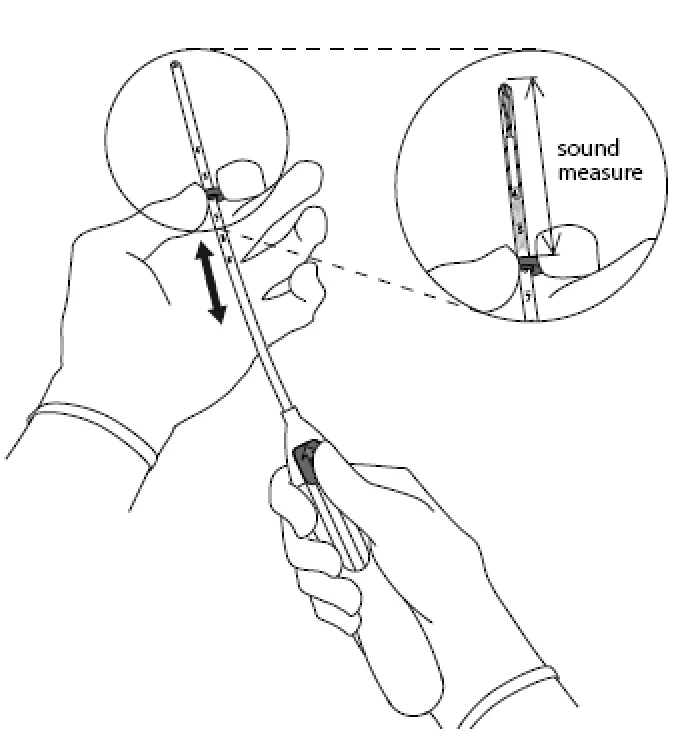
Holding the slider in the furthest position, set the upper edge of the flange to correspond to the sound measurement of the uterine depth (Figure 3).
Figure 3: Setting the Flange to the Uterine Depth
Step 4–MIRENA is now ready to be inserted
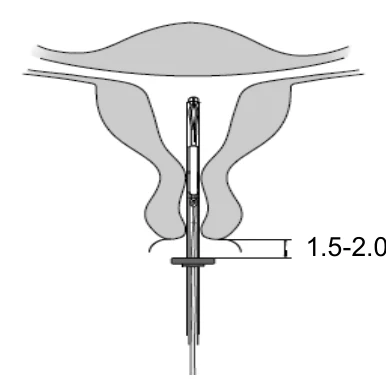
- While holding the slider in the furthest position, gently advance the inserter through the cervical canal and into the uterine cavity until the flange is approximately 1.5 to 2.0 cm from the external cervical os (Figure 4).
- NOTE: Do not advance flange to the cervix at this step. Maintaining the flange 1.5 to 2 cm from the cervical os allows sufficient space for the arms to open (when released) within the uterine cavity.
IMPORTANT! Do not force the inserter. If necessary, dilate the cervical canal.
Figure 4: Advancing the Inserter Until Flange is 1.5 to 2 cm From Cervical Os
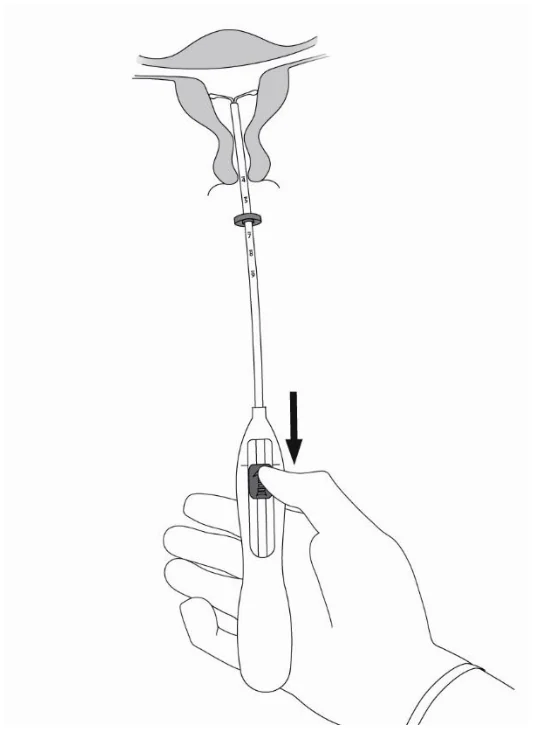
Step 5–Release the arms
While holding the inserter steady, pull the slider to the mark to open the horizontal arms of MIRENA (Figure 5). Wait approximately 10 seconds for the horizontal arms of MIRENA to open completely.
Figure 5: Releasing the Arms of MIRENA
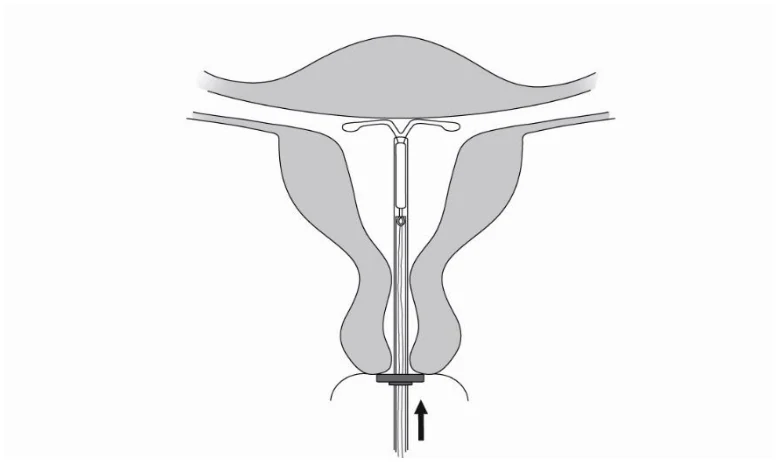
Step 6–Advance to fundal position
Advance the inserter gently towards the fundus of the uterus until the flange touches the cervix or you feel fundal resistance. MIRENA should now be in the desired fundal position (Figure 6).
1.5-2.0 cm
Figure 6: MIRENA in the Fundal Position
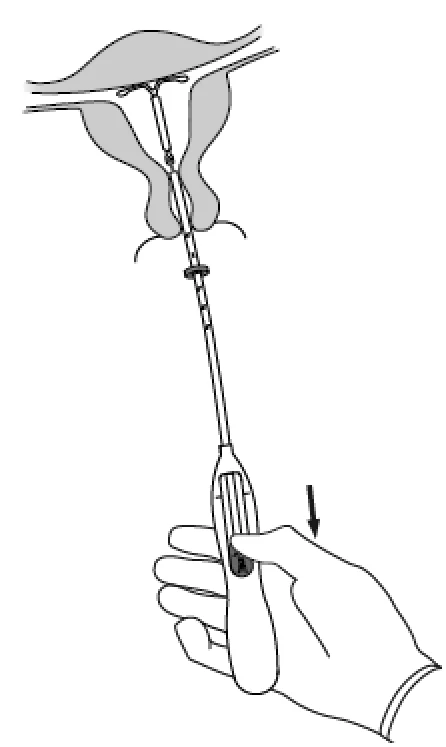
Step 7–Release MIRENA and withdraw the inserter
- While holding the inserter in place, pull the slider all the way down to release MIRENA from the insertion tube (Figure 7). The threads will release automatically from the internal thread lock of the inserter.
- Gently remove the inserter by pulling it out.
Cut the threads perpendicular to the thread length, for example, with sterile curved scissors, leaving about 2-3 cm visible outside of the cervix. NOTE: Cutting the threads at an angle may leave sharp ends.
Figure 7: Releasing MIRENA from the Insertion Tube
MIRENA insertion is now complete.
IMPORTANT!
If you suspect that MIRENA is not in the correct position, check placement (for example, with transvaginal ultrasound). Remove the system if it is not positioned properly within the uterine cavity. A removed system must not be re-inserted.
If there is clinical concern and/or exceptional pain or bleeding during or after insertion, appropriate and timely measures and assessments, for example ultrasound, should be performed to exclude perforation.
Users of MIRENA should be re-examined 4 to 12 weeks after insertion and once a year thereafter, or more frequently if clinically indicated.
Use of Sanitary Pads or Menstrual Cups
The use of sanitary pads is recommended. If tampons or menstrual cups are used, they should be changed carefully to avoid inadvertently pulling the MIRENA removal threads.
Removal/Replacement of MIRENA
Timing of Removal
- MIRENA should not remain in the uterus after 8 years. For conception control, remove MIRENA after 8 years of use. For idiopathic menorrhagia, remove MIRENA after 5 years of use.
- If pregnancy is not desired, the removal should be carried out during menstruation, provided the user is still experiencing regular menses. If removal will occur at other times during the cycle, consider starting a new contraceptive method a week prior to removal. If removal occurs at other times during the cycle and the user has had intercourse in the week prior to removal, they are at risk of pregnancy.
Tools for Removal
Preparation
- Gloves
- Speculum
Procedure
- Sterile forceps
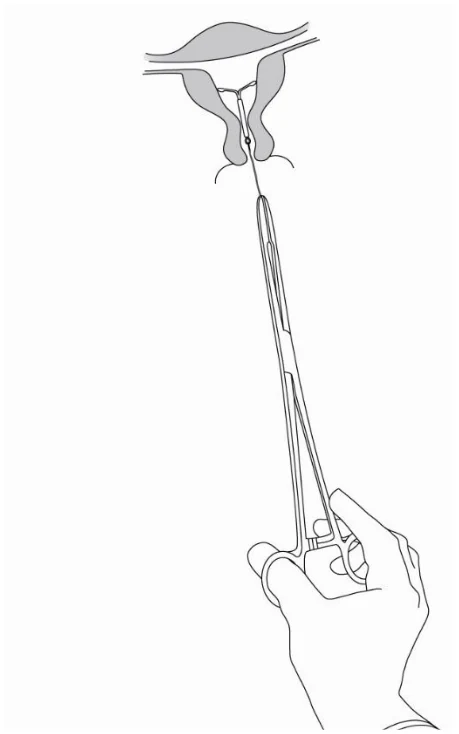
Removal Procedure
- Remove MIRENA by applying gentle traction on the threads with forceps (Figure 8).
- If the threads are not visible, determine location of MIRENA by ultrasound.
- If MIRENA is found to be in the uterine cavity on ultrasound exam, it may be removed using a narrow forceps, such as an alligator forceps. This may require dilation of the cervical canal. After removal of MIRENA, examine the system to ensure that it is intact.
Removal may be associated with:
- Some pain and/or bleeding or vasovagal reactions (for example, syncope, or a seizure in an epileptic individual).
- Breakage or embedment of MIRENA in the myometrium that can make removal difficult. Analgesia, paracervical anesthesia, cervical dilation, alligator forceps or other grasping instrument, or hysteroscopy may be used to assist in removal.
Replacement
If after 8 years for conception control, continued use of MIRENA is desired, a new MIRENA should be inserted immediately after the old one is removed.
MIRENA should be replaced if symptoms of idiopathic menorrhagia return. If after 5 years for idiopathic menorrhagia, continued use of MIRENA is desired, a new MIRENA should be inserted immediately after the old one is removed.
A replacement MIRENA can be inserted at any time during the menstrual cycle.
Figure 8: Removal of MIRENA
4.5 Missed Dose
MIRENA should be removed after 8 years for conception control and after 5 years for idiopathic menorrhagia. If the user wishes to continue using MIRENA, a new system can be inserted replacing the old system. If the system has been used for a longer period of time than 8 years for conception control, pregnancy should be ruled out before insertion of a new system.
5 Overdose
Not applicable. MIRENA is an intrauterine system.
For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844-POISON-X (1-844-764-7669).
6 Dosage Forms, Strengths, Compositions, and Packaging
Table 1: Dosage Forms, Strengths, and Composition
| Route of Administration | Dosage Form / Strength / Composition | Non-Medicinal Ingredients |
|---|---|---|
| Intra-uterine | Intrauterine system / 52 mg levonorgestrel (LNG) | barium sulphate, iron oxide, polydimethylsiloxane, polyethylene, silica |
Each MIRENA contains 52 mg of levonorgestrel in a cylindrical-shaped reservoir composed of a matrix of levonorgestrel and polydimethylsiloxane. The reservoir is mounted on the vertical arm of a T-shaped frame made of polyethylene and covered with a rate-controlling membrane of polydimethylsiloxane and silica. The white T-frame is pigmented with barium sulphate, which makes it visible in X-ray examination. Brown polyethylene removal threads attached to the T-frame are pigmented with black iron oxide.
MIRENA is in a sterile package within the EvoInserter (Figure 9). The EvoInserter, which is used for insertion of MIRENA into the uterine cavity, consists of a symmetric two-sided body and slider that are integrated with flange, lock, insertion tube and plunger. The outer diameter of the insertion tube is 4.4 mm. The vertical stem of MIRENA is loaded in the insertion tube at the tip of the inserter. The arms are pre-aligned in the horizontal position. The removal threads are contained within the insertion tube and handle. Once MIRENA has been placed, the inserter is discarded.
Figure 9: MIRENA EvoInserter
7 Warnings and Precautions
Please see the 3 Serious Warnings and Precautions Box at the beginning of Part I: Health Professional Information.
General
MIRENA should be used with caution in individuals who have migraine, focal migraine with asymmetrical visual loss or other symptoms indicating transient cerebral ischemia, severe headache, marked increase in blood pressure or active or previous severe arterial disease such as stroke or myocardial infarction (see 7 Warnings and Precautions – Cardiovascular; Hematologic; Neurologic). Removal of MIRENA should be considered if any of the above conditions occur during use.
Cases of breast cancer have been reported in users of MIRENA (see 7 Warnings and Precautions – Carcinogenesis and Mutagenesis).
MIRENA is intended for use only in individuals of child-bearing age.
MIRENA is not suitable for use as a postcoital contraceptive.
Insertion, Removal and Replacement Precautions
See 4 Dosage and Administration – Insertion, Removal and Replacement and Insertion Instructions.
Carcinogenesis and Mutagenesis
Breast Cancer
Cases of breast cancer have been reported in users of MIRENA (see 8 Adverse Reactions).
The incidence rate of breast cancer in association with MIRENA use has been analyzed in a large Finnish epidemiological study using hospital registry data and cancer diagnoses derived from the Finnish Cancer Registry. In this study, the incidence rate of breast cancer in 17,360 MIRENA users (a total of > 58,000 person years with MIRENA, and > 150,000 person years of follow-up) was not statistically significantly different compared to the occurrence of breast cancer in 4,863 control MIRENA non-users. In addition, the incidence rate of breast cancer among these MIRENA users has been compared to the average breast cancer incidence rates in Finland. There was no indication of a statistically significant difference between the MIRENA users and average Finnish female population in any of the age groups studied (30-54 years). Although these studies do not support a causal relationship between MIRENA and the development of breast cancer, an elevated breast cancer risk cannot be totally excluded, since these studies did not control for confounding factors such as use of oral hormonal contraception by control subjects, genetics and lifestyle and environmental factors such as smoking and alcohol.
Increasing age, inherited mutations, and a strong family history are the most significant risk factors for the development of breast cancer. Other established risk factors include nulliparity, first full-term pregnancy after the age of 30, menarche before the age of 12, never breastfed a child, and daily alcohol consumption. In some individuals, the use of hormonal contraceptives may accelerate the growth of an existing but undiagnosed breast cancer. More thorough studies are needed to determine the definitive link between hormonal contraceptive use and the potential risk of breast cancer. There is currently no conclusive evidence of an association between MIRENA use and development of breast cancer or progression of subclinical breast cancer. There is no reason to change prescribing habits at present.
Breast self-examination should be discussed with individuals receiving hormonal contraceptives. Individuals should be instructed to notify their healthcare professionals whenever any masses are detected.
Cardiovascular
An individual benefit-risk assessment in relation to continued use of MIRENA should be carried out in the event of arterial thrombosis. In particular, removal of MIRENA should be considered if severe arterial disease such as stroke or myocardial infarction occurs. In addition, MIRENA should be used with caution in individuals with a previous history of severe arterial disease such as stroke or myocardial infarction. Individuals with a history of thromboembolic disorders should be made aware of the possibility of a recurrence (see 7 Warnings and Precautions – Hematologic and 8 Adverse Reactions – 8.5 Post-Market Adverse Reactions). There have been postmarket reports of cardiovascular events, including myocardial infarction and stroke in MIRENA users, although a causal relationship with MIRENA could not be clearly established in these cases.
Predisposing Factors for Coronary Artery Disease
Cigarette smoking increases the risk of serious cardiovascular side effects and mortality. Hormonal contraceptives increase this risk, especially with increasing age.
Other individuals who are independently at high risk for cardiovascular disease include those with diabetes, hypertension, abnormal lipid profile, or a family history of these risk factors.
Hypertension
If a significant elevation of blood pressure in previously normotensive or hypertensive individuals occurs at any time during MIRENA use, MIRENA removal should be considered.
Congenital or Valvular Heart Disease
MIRENA should be used with caution in individuals with congenital or valvular heart disease who are at risk of infective endocarditis.
Driving and Operating Machinery
The effect of MIRENA on the ability to drive or use machines has not been studied. Users should be advised not to drive or use machines until they know how they react to MIRENA.
Endocrine and Metabolism
Glucose Tolerance
Combination and progestogen-only oral contraceptives, including those containing levonorgestrel, may affect glucose tolerance in some users. Diabetic individuals, and those with a family history of diabetes, should be observed closely to detect any alterations in carbohydrate metabolism. Young diabetic individuals whose disease is of recent origin, well controlled and not associated with hypertension or other signs of vascular disease such as ocular fundal changes, should be closely observed. One published clinical study indicated no change in mean daily insulin requirements in MIRENA users with Type 1 diabetes over a 12-month period.
Gastrointestinal
Gastrointestinal disorders have been reported (see 8 Adverse reactions – 8.2 Clinical Trial Adverse Reactions).
Genitourinary
Bleeding irregularities
Because irregular menstrual bleeding or spotting is common during the first few months of use, endometrial pathology should be excluded prior to insertion of MIRENA. Irregular bleeding patterns in users of MIRENA could mask the signs and symptoms of cervical or endometrial cancer. If bleeding irregularities develop after prolonged use, appropriate diagnostic measures should be undertaken.
Prolonged menstrual bleeding may occur during the first few months, however with continued use, bleeding patterns vary from regular scanty menstruation in some users to infrequent bleeding or amenorrhea in others. Infrequent bleeding and amenorrhea develop gradually in 57% and 16% of users during the first year of use, respectively. By the end of year 8 of MIRENA use, infrequent bleeding and amenorrhea are experienced by 26% and 34% of users, respectively. Reduced bleeding increases the level of blood hemoglobin. Hemoglobin and serum ferritin levels have been shown to increase after insertion of MIRENA among users with anemia due to heavy menstrual bleeding.
The possibility of pregnancy should be considered if menstruation does not occur after six weeks or more of amenorrhea, following a pattern of regular menses. A pregnancy test is not necessary in amenorrheic users unless indicated by other symptoms.
Hematologic
An individual benefit-risk assessment in relation to continued use of MIRENA should be carried out in the event of thrombosis. In particular, removal of MIRENA should be considered if venous thromboembolic disease such as deep vein thrombosis or pulmonary embolism occurs. Individuals with a history of thromboembolic disorders should be made aware of the possibility of a recurrence (see 7 Warnings and Precautions – Cardiovascular and 8 Adverse Reactions – 8.5 Post-Market Adverse Reactions). There have been postmarketing reports of arterial and venous thromboembolism (ATE, VTE) in MIRENA users, although a causal relationship with MIRENA could not be clearly established in such cases. Epidemiological studies have indicated that individuals using progestogen-only oral contraceptives may have a slightly increased risk of venous thromboembolism; however, the results are not statistically significant.
Appropriate diagnostic and therapeutic measures should be undertaken immediately if there are symptoms or signs of thrombosis in users of MIRENA. Symptoms of thromboembolism include: unilateral leg pain and/or swelling, sudden severe pain in the chest whether or not it radiates to the left arm, sudden breathlessness, sudden onset of coughing, any unusual severe prolonged headache, sudden partial or complete loss of vision, diplopia, slurred speech or aphasia, vertigo, collapse with or without focal seizure, weakness or very marked numbness suddenly affecting one side or part of the body, motor disturbances and acute abdomen. Symptoms or signs of retinal thrombosis are: unexplained partial or complete loss of vision, onset of proptosis or diplopia, papilledema, or retinal vascular lesions.
Other Risk Factors for Venous Thromboembolism
Other generalized risk factors for venous thromboembolism include but are not limited to a personal history, a family history (the occurrence of VTE in a direct relative at a relatively early age may indicate genetic predisposition), severe obesity (body mass index ≥30 kg/m2) and systemic lupus erythematosus. The risk of VTE also increases with age and smoking. The risk of VTE may be temporarily increased with prolonged immobilization, major surgery, or trauma. Also individuals with varicose veins and leg cast should be closely monitored.
Hepatic/Biliary/Pancreatic
Steroid hormones may be poorly metabolized in individuals with impaired liver function. Acute or chronic disturbances of liver function may necessitate the discontinuation of hormonal contraceptive use until markers of liver function return to normal (see 2 Contraindications).
To date, no studies have examined whether the avoidance of the first-pass effect through the liver, as with non-oral hormonal contraceptives, lessens concerns in individuals with liver conditions.
Jaundice
Individuals who have had jaundice should be given hormonal contraceptives only with great care and under close observation. If jaundice develops in an individual using MIRENA, consideration should be given to removing the system. Hormonal contraceptive-related cholestasis has been described in individuals with a history of pregnancy-related cholestasis. This condition may recur with subsequent hormonal contraceptive use (see 2 Contraindications).
Monitoring and Laboratory Tests
Physical Examination and Follow-up
See 4 Dosage and Administration – Medical Examination/Consultation.
Neurologic
Headache
MIRENA should be used with caution in individuals with a history of migraine headache, including migraine with focal neurological symptoms. The onset or exacerbation of migraine or the development of headaches with a new pattern that is recurrent, persistent or severe requires evaluation of the cause and consideration to remove MIRENA (see 7 Warnings and Precautions – General; Cardiovascular).
Ophthalmologic
Contact Lenses
Any eye problems or discomfort occurring during use of a hormonal contraceptive, including those relating to the use of contact lenses, should be assessed. If this occurs, an ophthalmologist should be consulted. Temporary or permanent cessation of wear may be advised.
Perioperative Considerations
Thromboembolic Complications – Postsurgery
MIRENA users who require surgery associated with prolonged immobilization should be followed closely for signs and symptoms of thromboembolism.
Psychiatric
Individuals with a history of emotional disturbances, especially the depressive type, may be more prone to have a recurrence of depression while using MIRENA. In cases of a serious recurrence, consideration should be given to removing MIRENA, since the depression may be drug-related.
Reproductive Health
Sexual Function/Reproduction
Ectopic Pregnancy
Individuals with a previous history of ectopic pregnancy, tubal surgery, or pelvic infection carry a higher risk of ectopic pregnancy. Carefully consider the possibility of an ectopic pregnancy in individuals who become pregnant while having MIRENA in place. Pregnancies with MIRENA use are rare, however, when a user becomes pregnant with MIRENA in situ, the relative likelihood of ectopic pregnancy is increased. Up to half of the pregnancies that occur with MIRENA in place are ectopic. The possibility of ectopic pregnancy should be considered in the case of lower abdominal pain, especially in association with missed periods, or if an amenorrheic user starts bleeding.
Individuals who choose MIRENA should be told about the risk of ectopic pregnancy, including the possibility of impaired fertility or loss of fertility. Educate users to recognize and report to their healthcare professional any signs and symptoms of ectopic pregnancy.
Combined data from prospective clinical trials with MIRENA reveal an overall rate of ectopic pregnancy of 0.06 per 100 person-years. A similar ectopic pregnancy rate has been reported in a postmarketing surveillance study with data from over 17,000 MIRENA users. In a large, prospective, comparative, non-interventional, cohort study with an observation period of 1 year, the ectopic pregnancy rate with MIRENA was 0.02 per 100 person-years.
Expulsion
Partial or complete expulsion of MIRENA may occur resulting in the loss of efficacy. Symptoms of the partial or complete expulsion of MIRENA may include bleeding or pain; however, a system may be expelled from the uterine cavity without the user noticing it. Since MIRENA decreases menstrual flow, an increase in menstrual flow may indicate an expulsion.
In a five-year clinical trial, the net cumulative expulsion rate ranged from 3.4 per 100 users in year one to 4.9 in year five. Expulsion rates for MIRENA are comparable to those observed for copper IUDs.
In a large, retrospective, cohort study (mean observation time of 2 years) in LNG IUS and copper IUD users (N=326,658), the overall incidence of expulsion was 2.74 per IUS/IUD insertions. The incidence of expulsion was 7.75 per 100 insertions among users with IUS/IUD insertion immediately after delivery (i.e., 0-3 days following delivery); and the incidence was 2.95 per 100 insertions among users without documented delivery in the past 52 weeks. The expulsion rate among users at other postpartum intervals were generally similar to that of users without delivery in the past 52 weeks. The risk of expulsion appears to be increased with insertions immediately after delivery (see 8 Adverse Reactions – 8.5 Post-Market Adverse Reactions) and appears to be increased after second-trimester abortion based on these limited data.
Analysis of expulsion risk factor among users who had not delivered within 12 months before insertion (228,834 users) showed an increased expulsion risk in:
- Users with history of heavy menstrual bleeding: the incidence of expulsion was 7.37 per 100 insertions in users with a recent history (≤ 12 months before insertion) and 9.24 per 100 insertions in users with both recent and past history (> 12 months), compared to users without any prior diagnosis of menorrhagia (2.10 expulsions per 100 insertions).
- Users with greater than normal BMI at the time of insertion: this risk increases gradually with increasing BMI. Compared to users with normal BMI (2.14 expulsions per 100 insertions), the incidence of expulsion was 5.39 per 100 insertions in users with morbid obesity (BMI≥40).
Users should be counselled on the possible signs of expulsion and how to check the threads of MIRENA. Advise them to contact their healthcare professional if the threads cannot be felt and avoid intercourse or use a barrier contraceptive (such as condoms) until the location of MIRENA has been confirmed. If expulsion is suspected based on ultrasound, consider further diagnostic imaging such as x-ray.
A partially expelled MIRENA should be removed. A new system can be inserted at that time provided pregnancy has been excluded.
The risk of expulsion may be increased when the uterus is not completely involuted at the time of insertion. Delay MIRENA insertion a minimum of six weeks or until uterine involution is complete following a delivery or a second trimester abortion.
Ovarian Cysts (Delayed Follicular Atresia)
Since the contraceptive action of MIRENA is due mainly to its local effect on the uterus, ovulatory cycles with follicular rupture usually occur in individuals of fertile age. Sometimes atresia of the follicle is delayed and folliculogenesis may continue. These enlarged follicles cannot be distinguished clinically from ovarian cysts.
Ovarian cysts have been reported as an adverse drug reaction in 6.8%-8.2% of MIRENA users when MIRENA was used as a contraceptive (duration of use from 1 to 5 years), and in 5.5%-10.4% of MIRENA users when MIRENA was used to treat menorrhagia (duration of use from 6 months to 5 years). In a large clinical trial (n=2,246), the rate of functional ovarian cysts was 1.2 per 100 person-years. Cysts are usually small and disappear spontaneously within a few months.
Most of these cysts are asymptomatic, although some may be accompanied by pelvic pain or dyspareunia. In most cases, the ovarian cysts disappear spontaneously over a two to three month period. Should this not occur, continued ultrasound monitoring and other diagnostic or therapeutic measures are recommended. Rarely, surgical intervention may be required.
Pelvic Infection
The inserter provided with MIRENA helps protect the system from contamination with micro-organisms during insertion, thereby minimizing the risk of pelvic infection. The exposed product should be handled with aseptic precautions (see 4 Dosage and Administration – Insertion Instructions). Known risk factors for pelvic inflammatory disease include multiple sexual partners, frequent intercourse and young age. Less common causes of pelvic inflammatory disease include pelvic actinomycosis and pelvic tuberculosis, both of which are extremely rare. In clinical trials, total combined upper genital infections were reported in 3.5% of MIRENA users. More specifically, endometritis was reported in 2.1%, pelvic inflammatory disease in 0.6%, and all other upper genital infections in ≤0.5% of users overall. These infections occurred more frequently within the first year. There is an increased risk of PID during 20 days following the insertion of IUDs related to the insertion procedure. Thereafter, the risk of PID during the use of IUDs or MIRENA is small. Users should be advised to report to their healthcare professionals promptly if they experience symptoms suggestive of PID.
If recurrent endometritis or pelvic infections are experienced, or if an acute infection does not respond to treatment within a few days, MIRENA must be removed.
Actinomycosis
Actinomycosis has been associated with IUDs. Remove MIRENA from symptomatic users and treat with antibiotics. The significance of actinomyces-like organisms on Pap smear in an asymptomatic IUD user is unknown, and so this finding alone does not always require MIRENA removal and treatment. When possible, confirm a Pap smear diagnosis with cultures.
Sepsis
There have been very rare postmarket reports of Group A streptococcal sepsis temporally associated with MIRENA insertion. Because death from Group A streptococcal (GAS) is more likely if treatment is delayed, it is important to be aware of these rare but serious infections. Aseptic technique during insertion of MIRENA is essential in order to minimize serious infections such as GAS.
Uterine Perforation
Partial perforation (uterine embedment) or complete perforation of the uterus wall or cervix may occur during insertion, although the perforation may not be detected until later. Pregnancy may result from partial or complete perforation. If partial or complete perforation occurs, MIRENA must be located and removed; surgery may be required. Partial perforation (uterine embedment) can result in difficult removal. Delayed detection of perforation may result in migration outside the uterine cavity, adhesions, peritonitis, intestinal perforation and obstruction, abscesses and erosion of adjacent viscera. The number of uterine perforations is linked to the experience of the person inserting the system. Removal of a perforated IUS was associated (in a few cases) with sliding/separating of the hormone cylinder. During clinical trials with MIRENA, perforation occurred at a rate between 0.1 and 1 per 1000 insertions. These clinical trials excluded breast-feeding individuals.
In a large, prospective, comparative, non-interventional, cohort study (1 year follow-up period) in MIRENA and copper IUD users (N = 61,448), the incidence of perforation was 1.3 (95% CI: 1.1 – 1.6) per 1000 insertions in the entire study cohort; 1.4 (95% CI: 1.1 – 1.8) per 1000 insertions in the MIRENA cohort and 1.1 (95% CI: 0.7 – 1.6) per 1000 insertions in the copper IUD cohort. Extending the observational period to 5 years in a subgroup of this study (N = 39,009 individuals using MIRENA or copper IUD), the incidence of perforation detected at any time during the entire 5-year period was 2.0 (95% CI: 1.6 – 2.5) per 1000 insertions; 2.1 (95% CI: 1.6 – 2.8) and 1.6 (95% CI: 0.9 – 2.5) for MIRENA and copper IUD, respectively.
The study showed that both breastfeeding at the time of insertion and insertion up to 36 weeks after giving birth were associated with an increased risk of perforation (see Table 2). These risk factors were confirmed in the subgroup followed up for 5 years. Both risk factors were independent of the type of IUD inserted.
Table 2: Incidence of perforation per 1000 insertions for the entire study cohort observed over 1 year, stratified by breastfeeding and time since delivery at insertion (parous individuals)
| Breastfeeding at time of insertion | Not breastfeeding at time of insertion | |
|---|---|---|
| Insertion ≤ 36 weeks after delivery | 5.6 (95% CI 3.9-7.9; n=6047 insertions) | 1.7 (95% CI 0.8-3.1; n=5927 insertions) |
| Insertion > 36 weeks after delivery | 1.6 (95% CI 0.0-9.1; n=608 insertions) | 0.7 (95% CI 0.5-1.1; n=41910 insertions) |
The risk of perforation may be increased in individuals with abnormal uterine anatomy or with fixed retroverted uteri.
To reduce the possibility of perforation postpartum, MIRENA insertion should be delayed a minimum of 6 weeks after delivery or until uterine involution is complete. If involution is delayed, consider waiting until 12 weeks postpartum. Inserting MIRENA immediately after first trimester abortion is not known to increase the risk of perforation, but insertion after second trimester abortion should be delayed until uterine involution is complete.
To reduce the possibility of perforation, it is important to follow the recommended insertion technique (see 4 Dosage and Administration – Insertion Instructions).
Inform individuals before the procedure about the risk of uterine perforation and educate them on possible signs of this complication, including, but not limited to, severe low abdominal pain, which may be associated with bleeding after the procedure, loss of threads, or change in thread length. Individuals with higher risk factors for uterine perforation should be carefully followed up. See 8 Adverse Reactions – 8.5 Post-Market Adverse Reactions for results from another large retrospective cohort study for risk factors of uterine perforation.
Uterine Embedment
Embedment of MIRENA in the myometrium may occur. Embedment may decrease contraceptive effectiveness and result in pregnancy. An embedded MIRENA must be removed. Embedment can result in difficult removal, and may require surgery.
Fertility: The use of MIRENA does not alter the course of future fertility. Upon removal of MIRENA, individuals return to their normal fertility (see 10 Clinical Pharmacology – 10.2 Pharmacodynamics).
Skin
Skin and subcutaneous tissue disorders have been reported (see 8 Adverse Reactions – 8.2 Clinical Trial Adverse Reactions).
7.1 Special Populations
7.1.1 Pregnancy/Intrauterine pregnancy
The use of MIRENA during an existing or suspected pregnancy is contraindicated (see also 2 Contraindications). If pregnancy occurs with MIRENA in place, MIRENA should be removed since any intrauterine system left in place may increase the risk of abortion and preterm labour. Removal of MIRENA or probing of the uterus may result in spontaneous abortion. In the event of an intrauterine pregnancy with MIRENA in place, consider the following:
- a) Risk of septic abortion
- b) Continuation of pregnancy
If MIRENA cannot be removed or the user chooses not to have it removed, they should be warned that failure to remove MIRENA increases the risk of miscarriage, sepsis, premature labor, and premature delivery. Ectopic pregnancy should be excluded. The user should be followed closely and advised to report any abnormal symptoms, such as fever, chill, cramping, abdominal pain, bleeding, vaginal discharge, or leakage of fluid.
- c) Long-term effects and congenital anomalies When pregnancy continues with MIRENA in place, long-term effects on the offspring are unknown. Congenital anomalies in live births have occurred infrequently. There have been few cases of masculinization of the external genitalia of the female fetus following local exposure to levonorgestrel during pregnancy with an LNG-IUS in place.
7.1.2 Breastfeeding
Hormonal contraceptives are not recommended as the contraceptive method of first choice in breast-feeding individuals. A published study indicated that during lactation, 0.1% of the daily maternal dose of levonorgestrel could be transferred to the newborn via milk. Although levonorgestrel has been found in the breast milk of MIRENA users, there does not appear to be a detrimental effect on growth or development of breast-fed infants whose mothers started using the product after six weeks postpartum. Progestogen-only contraceptive methods do not appear to affect the quantity and quality of breast milk. However, isolated cases of decreased milk production have been reported with MIRENA.
7.1.3 Pediatrics
Pediatrics (<18 years of age): No data are available to Health Canada; therefore, Health Canada has not authorized an indication for pediatric use.
7.1.4 Geriatrics
MIRENA has not been studied in individuals over the age of 65 years.
8 Adverse Reactions
8.1 Adverse Reaction Overview
The majority of MIRENA users experience changes in menstrual bleeding pattern after insertion of MIRENA. Over time, the frequency of amenorrhea and infrequent bleeding increases, and the frequency of prolonged, irregular and frequent bleeding decreases (see 7 Warnings and Precautions – Genitourinary: Bleeding irregularities; and 10 Clinical Pharmacology – 10.2 Pharmacodynamics).
The serious adverse reactions of ectopic pregnancy, intrauterine pregnancy, sepsis, pelvic inflammatory disease, perforation, expulsion and ovarian cysts are discussed in 7 Warnings and Precautions.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Adverse drug reactions (ADRs) were collected from a total of 3,754 study participants using MIRENA during 9 clinical trials in contraception (n=3422) and 10 clinical trials in menorrhagia (n=332), worldwide. The length of treatment varied between studies: from 3 months to 5 years in the MIRENA menorrhagia studies and from 1.5 months to 5 years in the MIRENA contraception studies.
ADRs were more common during the first months after insertion of MIRENA, and then gradually decreased over time. The ADR safety profile was consistent across the two indications.
Table 3: Number and Percentage of Participants (≥1.0%) with Treatment-related AEs (ADRs) by Preferred Terma – FAS for all Contraception and Menorrhagia Studies with MIRENA
| System organ class / preferred term | N= 3754 Very Common (≥10%) | N= 3754 Common (≥1% to <10%) |
|---|---|---|
| System organ class / preferred term | N= 3754 Very Common (≥10%) | N= 3754 Common (≥1% to <10%) |
| Gastrointestinal disorders | Abdominal pain Nausea Pelvic pain | |
| General disorders | Pain | |
| Infections and infestations | Vaginal infection | |
| Injury, poisoning, and procedural complications | Procedural pain | |
| Investigations | Weight increased | |
| Musculoskeletal and connective tissue disorders | Back pain | |
| Nervous system disorders | Headache | |
| Psychiatric disorders | Depression Libido decreased Nervousness | |
| Reproductive system and breast disorders | Amenorrhea Hypomenorrhea Menstrual disorder Metrorrhagia | Breast pain Breast tenderness Dysmenorrhea Genital hemorrhage IUD complication Menometrorrhagia Menorrhagia Menstruation irregular Oligomenorrhea Ovarian cyst Polymenorrhea Vaginal/genital discharge |
| Skin and subcutaneous tissue disorders | Acne Skin disorder |
- a MedDRA Version 11.0 coding
N=total number of participants;
Note: In original study reports causalities of related AEs are defined as ‘Yes’, ‘Possible’, ‘Probable’, or ‘Certain’
A separate study with 362 participants who have used MIRENA for more than 5 years showed a consistent adverse reaction profile in years 6 through 8 as shown in Table 3. By the end of year 8 of use, amenorrhea and infrequent bleeding were experienced by 34% and 26% of users, respectively; irregular bleeding occurred in 10%, frequent bleeding in 3%, and prolonged bleeding in 3% of users. In this study, 9% of participants reported the adverse event of weight gain; it is unknown if the weight gain was caused by MIRENA.
8.3 Less Common Clinical Trial Adverse Reactions
Not applicable
8.4 Abnormal Laboratory Findings: Hematologic, Clinical Chemistry and other Quantitative Data
Not applicable
8.5 Post-Market Adverse Reactions
The most commonly occurring adverse events (i.e., in greater than 10% of users) that are observed post marketing with MIRENA are uterine/vaginal bleeding (including frequent, prolonged or heavy bleeding, spotting, oligomenorrhea, amenorrhea) and benign ovarian cysts.
In a large, prospective, comparative, non-interventional, cohort study (1 year follow-up period) in MIRENA and copper IUD users (N = 61,448), the incidence of perforation was 1.3 (95% CI: 1.1 - 1.6) per 1000 insertions in the entire study cohort; 1.4 (95% CI: 1.1 - 1.8) per 1000 insertions in the MIRENA cohort and 1.1 (95% CI: 0.7 - 1.6) per 1000 insertions in the copper IUD cohort. This study showed that breastfeeding at the time of insertion and insertion up to 36 weeks after giving birth are independent risk factors for perforation (see 7 Warnings and Precautions – Sexual Function/Reproduction: Uterine Perforation).
In a large retrospective cohort study (mean observation time of 2 years) in LNG IUS and copper IUD users (N=326,658) the impact of breastfeeding and timing of postpartum IUD insertion on uterine perforation and IUD expulsion was assessed. For uterine perforation, the study results indicated that the risk of uterine perforation was highest in participants with IUD insertion ≤ 6 weeks postpartum. Immediate postpartum insertion (0–3 days) findings are limited due to the relatively small number of insertions occurring within this time interval. Participants who were breastfeeding at the time of insertion were at 33% higher risk of perforation (adjusted hazard ratio [HR]=1.33, 95% confidence interval [CI]: 1.07–1.64) compared to participants who were not breastfeeding at the time of insertion. Progressively lower risk of uterine perforation was observed in postpartum time windows beyond 6 weeks, in both breastfeeding and not breastfeeding participants. For expulsion, the study showed that the risk of expulsion is increased in participants with history of heavy menstrual bleeding, and in participants with greater than normal BMI at the time of insertion; this risk increases gradually with increasing BMI. The study also showed that the risk of expulsion is increased with insertions immediately after delivery (i.e., 0-3 days following delivery) (see 7 Warnings and Precautions – Sexual Function/Reproduction; Expulsion).
Undesirable effects are more common during the first months after insertion and subside during prolonged use. In addition to the adverse events observed in clinical trials, the following undesirable effects have been reported in users of MIRENA, although a causal relationship with MIRENA could not always be confirmed.
Table 4: Adverse Reactions Identified in Postmarketing Surveillance
| Gastrointestinal disorders: | abdominal bloating |
| General disorders and administration site conditions: | expulsion, device breakage |
| Investigations: | blood pressure increased |
| Nervous system disorders | migraine |
| Reproductive system and breast disorders: | breast cancer, breast tension, mastalgia, pelvic pain, uterine perforation |
| Skin and subcutaneous disorders: | chloasma, hirsutism, alopecia, hypersensitivity including rash, pruritis, urticaria and angioedema |
Device breakage has been reported with the use of MIRENA. This can occur with MIRENA in place or during its removal. The broken pieces should be located and removed; surgery may be required. Check device integrity when removing MIRENA.
Isolated postmarketing cases of decreased milk production have been reported in individuals using a LNG-IUS.
The removal threads may be felt by the partner during intercourse.
The following ADRs have been reported in connection with the insertion or removal procedure of MIRENA: procedural pain, procedural bleeding, insertion-related vasovagal reaction with dizziness or syncope. The procedure may precipitate a seizure in an epileptic individual.
9 Drug Interactions
9.2 Drug Interactions Overview
The prescribing information of concomitant medications should be consulted to identify potential interactions.
9.3 Drug-Behaviour Interactions
The effect of MIRENA on the ability to drive or to use machines has not been studied. Users should be advised not to drive or use machines until they know how they react to MIRENA.
9.4 Drug-Drug Interactions
No drug-drug interaction studies have been conducted with MIRENA.
The effect of hormonal contraceptives may be impaired by drugs which induce liver enzymes, specifically cytochrome P450 enzymes. The influence of these drugs on the efficacy of MIRENA has not been studied, but it is not believed to be of major importance due to the local action of MIRENA.
Substances increasing the clearance of levonorgestrel
Substances which may increase the clearance of levonorgestrel include phenytoin, barbiturates, primidone, carbamazepine, rifampicin, and possibly also oxcarbazepine, topiramate, and products containing St. John’s wort.
Substances with variable effects on the clearance of levonorgestrel
When co-administered with sex hormones, many HIV/HCV protease inhibitors and non-nucleoside reverse transcriptase inhibitors can increase or decrease plasma concentrations of the progestin.
Substances decreasing the clearance of levonorgestrel (enzyme inhibitors)
Strong and moderate CYP3A4 inhibitors such as azole antifungals (e.g., fluconazole, itraconazole, ketoconazole, voriconazole), verapamil, macrolides (e.g., clarithromycin, erythromycin), diltiazem and grapefruit juice can increase plasma concentrations of the progestin.
9.5 Drug-Food Interactions
Interactions with food have not been established.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Interactions with laboratory tests have not been established.
Tissue Specimens
Pathologists should be advised of MIRENA therapy when specimens obtained from surgical procedures and Pap smears are submitted for examination.
10 Clinical Pharmacology
10.1 Mechanism of Action
MIRENA consists of a small polyethylene T-shaped frame with a cylindrical reservoir containing levonorgestrel around the vertical arm of the T frame (Figure 10). MIRENA is a long acting reversible contraceptive (LARC). After insertion into the uterus, MIRENA releases levonorgestrel continuously for up to eight years. Intrauterine administration allows a very low daily dosage, as the hormone is released directly to the target organ. MIRENA contains a total of 52 mg levonorgestrel. The in vivo levonorgestrel release rate 24 days after insertion is approximately 21 mcg per day, decreasing continuously to approximately 19 mcg per day after 1 year, to 11 mcg per day after 5 years and to 7 mcg per day after 8 years of use (see Table 7). MIRENA does not contain any estrogen.
Figure 10: MIRENA (levonorgestrel-releasing intrauterine system)
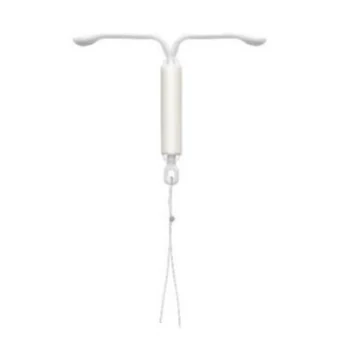
polyethylene T-shaped frame
cylindrical reservoir containing levonorgestrel
polyethylene removal threads
10.2 Pharmacodynamics
The contraceptive action of MIRENA is due mainly to the local progestogenic effect of levonorgestrel on the uterine cavity. It produces a strong antiproliferative effect on the endometrium and causes a thickening of the cervical mucus which prevents passage of sperm through the cervical canal. Ovulation is inhibited in some users. Clinical trials with MIRENA were performed in parous participants mainly over the age of 18 years; results from these studies involving more than 7,600 person-years of use indicate an overall Pearl index of 0.11. The 5-year cumulative gross pregnancy rates in these trials ranged from 0 to 1.2 per 100 participants.
Normal menstruation returns quickly after removal of MIRENA. After 5 years of use in clinical trials, the return of normal cyclical endometrial morphology was observed to occur from 1 to 3 months after removal of MIRENA. The use of MIRENA does not alter the course of future fertility; upon removal of MIRENA, individuals return to their normal fertility. Users requesting the removal of MIRENA for reasons of planning a pregnancy were followed for 24 months. During the 24-month period, nearly 90% of these individuals were able to get pregnant.
The duration and volume of menstrual bleeding and menstrual blood loss gradually decreases during the first few months of use. With continued use, bleeding patterns vary from regular scanty menstruation in some users to oligomenorrhea or amenorrhea in others.
During the first 90 days, prolonged bleeding is experienced by 22% and irregular bleeding by 67% of users after postmenstrual insertion of MIRENA, decreasing to 3% and 19% at the end of the first year of use, respectively. Concomitantly, amenorrhea is experienced by 0% and infrequent bleeding by 11% during the first 90 days, increasing to 16% and 57% at the end of the first year of use, respectively (Table 5). Reduced bleeding has been shown to increase the level of blood hemoglobin and ferritin in users who have anemia from heavy menstrual bleeding.
Table 5: Percentage of participants meeting the criteria for different patterns of bleeding during the first 90 days and at the End of Year 1
| MIRENA | First 90 days | End of year 1 |
|---|---|---|
| Amenorrhea | 0 % | 16 % |
| Infrequent bleeding | 11 % | 57 % |
| Frequent bleeding | 13 % | 1 % |
| Prolonged bleeding | 22 % | 3 % |
| Irregular bleeding | 67 % | 19 % |
The menstrual bleeding patterns of 1,495 participants enrolled in a clinical trial were examined for the first 12 months after MIRENA insertion. The number of combined days of vaginal bleeding or spotting decreased from a mean of 16.1 days during the first month, to a mean of 3.8 days during the 12th month (see Table 6).
Table 6: Number of Combined Vaginal Bleeding / Spotting Days During the first 12 Months After MIRENA Insertion
Interval (in 30-Day Segments) Days | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 1 - 30 | 31 - 60 | 61 - 90 | 91 - 120 | 121 - 150 | 151 - 180 | 181 - 210 | 211 - 240 | 241 - 270 | 271 - 300 | 301 - 330 | 331 - 360 | |
| N | 1,495 | 1,472 | 1,422 | 1,297 | 1,237 | 1,199 | 1,168 | 1,142 | 1,113 | 1,079 | 1,055 | 988 |
| mean | 16.1 | 11.2 | 8.5 | 7.1 | 6.4 | 5.8 | 5.2 | 4.8 | 4.5 | 4.3 | 4.1 | 3.8 |
The altered menstrual bleeding pattern that occurs with MIRENA use is a result of the direct action of levonorgestrel on the endometrium and is not due to the suppression of the ovulatory cycle. There is no clear difference in follicle development, ovulation, or estradiol and progesterone production in users with different bleeding patterns. Ovarian function is normal and estradiol levels are maintained even when users of MIRENA are amenorrheic.
The effect of MIRENA on ovarian function depends on plasma levonorgestrel levels achieved. While marked interindividual variation is observed, plasma concentrations are relatively constant within each individual. Patterns of ovarian function in MIRENA users include normal ovulatory cycles, anovulatory cycles with some inhibition of estradiol production, anovulation with high follicular activity and ovulation with an inadequate luteal phase. In general, anovulatory cycles correlate with higher plasma levels of levonorgestrel, and are more frequent in the first year of MIRENA use. Functional ovarian cysts may occur in relation to preovulatory arrest of follicular development in any individual, and are associated with progestogen-only methods of contraception.
Endometrial histology has been investigated in clinical studies examining the intrauterine release of levonorgestrel at rates ranging from 10 to 40 mcg/day. Participants with anywhere from 3 to 84 months of exposure to continuous levonorgestrel release showed endometrial glandular atrophy and decidualized stroma throughout the period. Local inflammation and focal necrosis compatible with the intrauterine mode of administration were observed.
In one study, cervical histology was evaluated by examining cervical smears from 1,355 participants using MIRENA over a period of five years. A total of twelve smears indicated moderate to severe cervical dysplasia. Large multicentre studies have not detected differences in cervical cytology between participants using MIRENA and those using copper IUDs.
10.3 Pharmacokinetics
Absorption
The intrauterine release of levonorgestrel results in the absorption of the drug into the systemic circulation. More than 90% of the released levonorgestrel is systemically available. Estimated in vivo release rates of levonorgestrel from MIRENA for different points in time are provided in Table 7.
Table 7: Estimated in vivo release rates of LNG from MIRENA
| Time | Estimated in vivo release rate [micrograms/day] |
|---|---|
| 24 days after insertion | 21 |
| 1 year after insertion | 19 |
| 3 years after insertion | 14 |
| 5 years after insertion | 11 |
| Average over 5 years | 15 |
| 8 years after insertion | 7 |
| Average over 8 years | 13 |
After insertion of MIRENA, levonorgestrel is detectable in serum/plasma after 1 hour. The maximum concentration is reached within 2 weeks after insertion and amounts to about 180 pg/ml (CV 38.3%). Following intrauterine insertion of MIRENA, the in vivo release rate of levonorgestrel is 21 mcg per day 24 days post insertion. In correspondence with the declining release rate, the geometric serum/plasma concentration of levonorgestrel declines continuously as shown in Table 8.
Table 8: Estimated Total LNG plasma concentrations
| Time after insertion | Total LNG plasma concentrations [pg/ml] (geometric CV%) |
|---|---|
| 24 days | 175 (37.6) |
| 2 months | 169 (37.1) |
| 1 year | 159 (37.4) |
| 3 years | 139 (37.8) |
| 5 years | 123 (38.2) |
| 8 years | 100 (39.9) |
Because of the low drug levels in plasma, the systemic effects of the progestogen are minimized.
Distribution
Levonorgestrel is bound to serum albumin and to sex hormone-binding globulin (SHBG). The relative distribution (free, albumin-bound, SHBG-bound) depends on the SHBG concentration in the serum. Less than 2% of the total serum drug levels are present as free steroid. Levonorgestrel binds with high affinity to SHBG. Accordingly, changes in the concentration of SHBG in serum result in an increase (at higher SHBG concentrations) or in a decrease (at lower SHBG concentrations) of the total levonorgestrel concentration in serum. The concentration of SHBG declined on average by about 20% during two months after insertion of MIRENA and remained stable thereafter, increasing only slightly until the end of the 8 years of use.
For levonorgestrel, the mean apparent volume of distribution is about 106 L.
Metabolism
Levonorgestrel is extensively metabolized. The most important metabolic pathways are the reduction of the Δ4-3-oxo group and hydroxylations at positions 2α, 1β and 16β, followed by conjugation. CYP3A4 is the main enzyme involved in the oxidative metabolism of levonorgestrel. The available in vitro data suggest that CYP mediated biotransformation reactions may be of minor relevance for levonorgestrel compared to reduction and conjugation.
The terminal half-life in serum is in the range of 14 to 20 hours after single-dose administration.
Elimination
Levonorgestrel is excreted as metabolites at about equal proportion in urine and feces. The metabolites have little or no pharmacological activity. The principal metabolite in urine is tetrahydronorgestrel which accounts for approximately 25% of the radioactivity recovered from the urine after administration of radiolabeled levonorgestrel. A published study indicated that during lactation, 0.1% of the daily maternal dose of levonorgestrel could be transferred to the newborn via milk.
Special populations and conditions
- Pediatrics (< 18 years of age): Controlled clinical trials were done in previously parous individuals aged mainly over 18 years. Use of this product before menarche is not indicated.
- Geriatrics: MIRENA has not been studied in individuals over the age of 65 years.
- Sex: MIRENA is intended for use only in individuals with a uterus, of reproductive age.
Pregnancy and breastfeeding
- Pregnancy: MIRENA is not indicated for use in pregnancy (see also 2 Contraindications and 7 Warnings and Precautions – 7.1 Special Populations: 7.1.1 Pregnancy/Intrauterine Pregnancy).
- Breast-feeding: Progestogen-only contraceptive methods do not appear to affect the quantity and quality of breast milk (see also 7 Warnings and Precautions – 7.1 Special Populations: 7.1.2 Breast-feeding).
- Hepatic Insufficiency: MIRENA is contraindicated in individuals with acute liver disease or liver tumors (see also 2 Contraindications and 7 Warnings and Precautions)
- Renal Insufficiency: MIRENA has not been studied in individuals with renal impairment.
- Obesity: Risk of expulsion is increased in individuals with greater than normal BMI at the time of insertion; this risk increases gradually with increasing BMI (see also 7 Warnings and Precautions – Sexual Function/Reproduction: Expulsion).
11 Storage, Stability, and Disposal
Store at room temperature (between 15°C and 30°C). Protect from moisture and direct sunlight.
Keep out of reach of children and pets.
Used MIRENA systems should be considered biohazardous waste. Care should be taken to ensure the remaining hormonal ingredients are not introduced into water/sewer systems.
12 Special Handling Instructions
MIRENA should be handled with aseptic precautions. Used MIRENA systems should be considered biohazardous waste.
Part 2: Scientific Information
13 Pharmaceutical Information
Drug Substance
Non-proprietary name of the drug substance:
Levonorgestrel
Chemical name:
18,19-Dinorpregn-4-en-20-yn-3-one, 13-ethyl-17-hydroxy-,(17α)(-)
Molecular formula and molecular mass:
C21 H28 O2
312.45
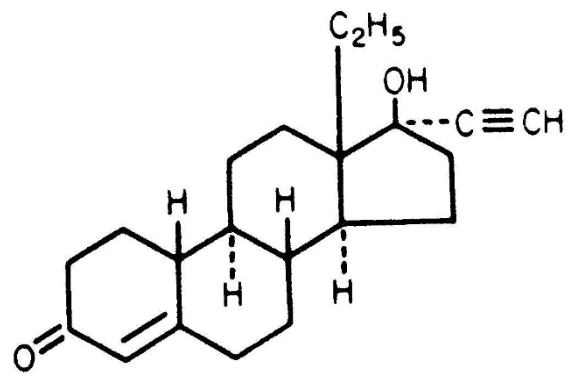
Structural formula:
Physicochemical properties:
Levonorgestrel is a white to off-white crystalline powder, practically insoluble in water and slightly soluble in ethanol, in vegetable oils, in chloroform, in ether and in alkaline solutions. The melting range is between 232°C and 239°C.
14 Clinical Trials
14.1 Clinical Trials by Indication
Contraception
Clinical studies with MIRENA (levonorgestrel-releasing intrauterine system) consistently show high contraceptive efficacy. The contraceptive efficacy of MIRENA was studied in three clinical trials in which a total of 2,379 participants were enrolled. One trial compared MIRENA (n=1,821) to a copper IUD (n=937) over a period of 5 years with a resultant Pearl index of 0.09 for MIRENA and 1.26 for the copper IUD. After completion of this trial, 168 participants from the MIRENA group enrolled in a second clinical trial and had a new MIRENA system inserted for four years. Results after 6,404 person-months of experience revealed a Pearl index of 0 (zero). A third MIRENA trial was noncomparative and enrolled 390 participants for 5 years with a resultant Pearl index of 0.24. Combined data from three clinical trials provides 91,133 person-months of experience. There were a total of 8 pregnancies, giving a Pearl Index of 0.11, representing approximately 99.9% efficacy.
The contraceptive efficacy of MIRENA during extended use beyond 5 years was studied in the MIRENA Extension Trial, a multi-center, open-label, uncontrolled study conducted in the United States. The trial enrolled participants 18 to 35 years of age who had been using MIRENA for not less than 4.5 years and not more than 5 years at enrollment. The population consisted of 362 participants using MIRENA. Of these 47.2% were nulliparous. The study population was predominantly White (75.4%); 14.1% of the participants were Black/African American, and 2.5% were Asian. The weight range was 38.5–163.5 kg (mean weight: 75.6 kg) and mean BMI was 27.9 kg/m2 (range: 15.4–57.7 kg/m2).
The pregnancy rate calculated as the Pearl Index (PI) was the primary efficacy endpoint used to assess contraceptive efficacy. The PI was based on 28-day equivalent exposure cycles; evaluable cycles excluded those in which back-up contraception was used unless a pregnancy occurred in that cycle. The PI for the 6th year of use based on the 1 pregnancy that occurred during Year 6 and within 7 days after MIRENA removal or expulsion and 3,870 evaluable cycles was 0.34 with a 95% upper confidence limit of 1.88 and the PI for the 7th year of use based on the 1 pregnancy that occurred during Year 7 and within 7 days after MIRENA removal or expulsion and 3,232 evaluable cycles was 0.40 with a 95% upper confidence limit of 2.25. The PI for the 8th year of use based on no pregnancies occurring during Year 8 and within 7 days after MIRENA removal or expulsion and 2,534 evaluable cycles was 0.00 with a 95% upper confidence limit of 1.90.
The cumulative 3-year pregnancy rate for Years 6, 7 and 8 was estimated by the Kaplan-Meier method. Based on 2 pregnancies (1 in Year 6 and 1 in Year 7) and 10,216 exposure cycles, the cumulative pregnancy rate at the end of the 3-year period of extended use (Years 6,7 and 8) was 0.68% with a 95% upper confidence limit of 2.71%.
Treatment of Idiopathic Menorrhagia
The pivotal menorrhagia study was a prospective, randomized, active-controlled, multicenter study in participants randomized to MIRENA or medroxyprogesterone acetate (MPA; 10 mg given orally, once daily for 10 consecutive days starting on the 16th day of each menstrual cycle) over 6 cycles. Participants with a normal length of menstrual cycle consisting of 21 to 35 days and withdrawal bleeding with menstrual blood loss (MBL) >80 mL measured at baseline were included in the study. Efficacy of both treatments was demonstrated using the objective alkaline hematin method for measuring MBL. The primary efficacy variables were the absolute change in MBL from baseline to the end-of-study and the proportion of participants with successful treatment. Successful treatment was defined as end-of-study MBL < 80 mL and a decrease in value of > 50% of baseline MBL.
Table 9: Summary Demographics in Menorrhagia Pivotal Trial
| Study Number | Trial Design | Study Drug | Duration | No. of Participantsa | Mean Age years (range) |
|---|---|---|---|---|---|
| 309849 | Open-label, randomized, multicenter, parallel | Test product: MIRENA 52 mg (20 mcg/24 hrs) | 6 cycles | N=82 | 38.3 (26 – 50) |
| 309849 | Open-label, randomized, multicenter, parallel | Comparator: Medroxyprogesterone acetate 10 mg po od administered for 10 consecutive days beginning on the 16th day of the menstrual cycle | 6 cycles | N=83 | 39.3 (26 – 53) |
No.=number; od=once daily; po=oral administration
- a FAS=full analysis set
Study Results
MIRENA was found to be superior to MPA for reductions in median MBL from baseline to end-of-study (P<0.001) (see Table 10). The proportion of participants who achieved successful treatment was also statistically and clinically significant in favor of the MIRENA treatment group (see Table 11).
Table 10: MIRENA vs MPA, The Absolute Change in MBL from Baseline to End-of-Study - Study 309849, FAS
Treatment Group | N | Median Baseline MBL (mL) [range] | Median End-of-Study MBL (mL) [range] | Change from Baseline to End-of-Study (mL) [range] | P-valuea Between Treatment Groups |
|---|---|---|---|---|---|
| MIRENA | 79 | 147.96 [68.3 to 431.4] | 7.10 [0.0 to 1435.6] | -128.78 [-393.6 to 1242.2b] | P < 0.001 |
| MPA | 81 | 154.20 [63.4 to 456.0] | 121.47 [0.0 to 437.7] | -17.77 [-271.5 to 78.6] | P < 0.001 |
FAS=full analysis set; MPA = medroxyprogesterone acetate tablets; N=number of participants; primary analysis set for efficacy
- a Statistical test: Wilcoxan-test. Significance level of the statistical test is 0.05 (two-sided).
- b
One subject experienced heavy blood loss thought to have resulted from the expulsion of MIRENA.
Table 11: MIRENA vs MPA, The Proportion of Participants with Successful Treatmenta - Study 309849, FAS
| Assessment | MIRENA N=82 (n) [%] | MPA N=83 (n) [%] | % Difference between treatment groups | 95% CI | P-valueb Between Treatment Groups |
|---|---|---|---|---|---|
| Successful Treatment | 67 (84.8%) | 18 (22.2%) | 62.59 | 50.56 – 74.61 | P < 0.001 |
| End-of-Study MBL < 80 mL | 71 (87.7%) | 24 (29.6%) | 58.02 | 45.77 – 70.28 | P < 0.001 |
| Decrease in End-of-Study MBL > 50% of Baseline MBL | 67 (84.8%) | 22 (27.2%) | 57.65 | 45.14 | P < 0.001 |
CI=confidence interval; FAS=full analysis set, primary analysis set for efficacy; MPA=medroxyprogesterone acetate tablets; N=number of participants
- a Successful treatment is defined as: End-of Study MBL < 80 mL and decrease in End-of-Study MBL > 50% of Baseline MBL
- b Statistical test: Pearson’s Chi-squared test. Significance level of the statistical test is 0.05 (two-sided).
Continuation Rate
The continuation rate for MIRENA in a five-year clinical trial in 390 participants was 56%. The desire to become pregnant was the most common reason for discontinuing MIRENA (about 20% of all discontinuations). Other discontinuations were due to medical reasons (predominantly hormonal, menstrual problems, and pain).
General Information
The following table gives typical pregnancy rates for various forms of birth control, including no birth control. The reported rates represent the number of individuals out of 100 who would become pregnant within the first year of use.
Table 12: Reported Pregnancies per 100 Individuals Within the First Year of Use
| Hormonal Intrauterine system (IUS) | less than 1 |
|---|---|
| Copper Intrauterine device (IUD) | less than 1 |
| Subdermal Implant | less than 1 |
| Progesterone Injection | 6 |
| Combined hormonal contraceptive (pill, patch or ring) | 9 |
| Diaphragm | 12 |
| Male condom | 18 |
| Female condom | 21 |
| Sponge, spermicide | 12-28 |
| Withdrawal method | 22 |
| Natural family planning | 24 |
| No method | 85 |
16 Non-Clinical Toxicology
Toxicology studies were performed on all the components of MIRENA: the "unfilled polymer", the "levonorgestrel-releasing reservoir", the "membrane tubing", the polyethylene "T-body" and the polyethylene "removal threads".
The unfilled polymer is the polydimethylsiloxane (PDMS) polymer after peroxide catalysis. The unfilled polymer is mixed in an equal ratio with levonorgestrel, to form the levonorgestrel-releasing reservoir. The unfilled polymer is also mixed with inert colloidal silica to form the membrane tubing, which covers the levonorgestrel reservoir and serves to control the release rate of levonorgestrel from MIRENA.
Acute toxicology
The USP systemic injection test in mice on the unfilled polymer, membrane tubing, T-body and removal threads did not show any signs of toxicity.
Mutagenicity
Extracts of the unfilled polymer, membrane tubing, T-body and removal threads were evaluated for mutagenic potential in the following in vitro and in vivo tests: reverse gene mutation in vitro in four Salmonella typhimurium and one Escherichia coli strains of bacteria, TK mutation test in mouse lymphoma L5178Y cells in vitro, chromosomal aberrations in human peripheral blood lymphocytes in vitro, and the induction of micronuclei in the bone marrow of mice.
Extracts of the unfilled polymer did not show any evidence of mutagenic or clastogenic activity in vitro and did not induce chromosomal changes or other damage to micronucleus formation in polychromatic erythrocytes in vivo after intraperitoneal administration to mice.
Saline and aqueous extracts of the levonorgestrel-releasing reservoir were negative except for the chromosomal aberration test in CHO cells. Treatment of cultures of CHO cells with the highest dose of DMSO extracts of the levonorgestrel-releasing reservoir, which were also precipitating, resulted in small increases in the number of cells with aberrations (attributed to polyploidy) in a single culture at the 20 and 44 hour sampling times during the second of two independent experiments. Pure levonorgestrel was not mutagenic or clastogenic in any of the tests. No clastogenic effect was detected for saline or arachis oil extracts tested in vivo in the mouse micronucleus test. The results of these studies indicate that it is very unlikely that the materials used in the levonorgestrel-releasing reservoir of MIRENA would cause genetic damage in humans under the conditions of clinical use.
Saline and nonaqueous extracts of the T-body containing low-density polyethylene (with 20%-24% barium sulphate), and of removal threads containing high-density polyethylene (with 1% iron oxide) were not mutagenic or clastogenic in vitro and did not induce chromosomal changes or other damage to micronucleus formation in polychromatic erythrocytes in vivo after intraperitoneal administration to mice.
Local tolerance studies
Saline and nonaqueous extracts of the unfilled polymer, membrane tubing, T-body and removal threads were evaluated for biocompatibility using the following in vitro and in vivo test systems: cytotoxicity test in mouse fibroblasts, guinea pig maximization test, intracutaneous test in rabbits, systemic injection test in mice, pyrogen testing, muscle implantation test in rabbits and a test for hemolysis.
The results of these tests indicated acceptable biocompatibility of both the unfilled polymer and the membrane tubing. No remarkable in vitro cytotoxicity or hemolysis was detected. There was no evidence of delayed contact hypersensitivity, intracutaneous injection site irritation or test article-related clinical signs of systemic toxicity including pyrogenicity, after treatment with saline or sesame oil extracts.
In the muscle implantation test for the unfilled polymer, very thin encapsulation was observed on the test article implants and in one of the negative control implants. This was correlated with minimal microscopic changes (few to moderate inflammatory cells) in both test and control implants, indicating that the unfilled polymer was well tolerated.
A similar result was observed in the muscle implantation test for the membrane tubing, a very thin encapsulation of the test and control implants which was detected at necropsy on Day 90 was correlated with minor microscopic changes (fibrosis), indicating that the membrane tubing was well tolerated.
With regard to the low-density polyethylene T-body, no remarkable in vitro cytotoxicity or hemolysis was detected. There was no evidence of delayed contact hypersensitivity, intracutaneous injection site irritation or test article-related clinical signs of systemic toxicity, including pyrogenicity after treatment with saline or sesame oil extracts. In the muscle implantation test for the T-body, a very thin encapsulation of one test article implant which was detected at necropsy on Day 90 was correlated with only minor microscopic changes (minimal to slight fibrosis, minimal necrosis and minimal hemorrhage). The same test for the removal threads showed a very thin encapsulation of the test article and USP negative control plastic implants which were detected at necropsy on Day 90, and were correlated with only minor histology (minimal to slight fibrosis). The results of these tests indicate that both the T-body and the removal thread were well tolerated.
Long-term toxicity
A one-year intrauterine toxicity study of MIRENA was conducted in Rhesus monkeys using a smaller modified version of the system delivering 12.3 mcg levonorgestrel per day. The raw materials were the same as those used in the formulation of MIRENA with the exception that the polydimethylsiloxane polymer was catalyzed using stannous octoate rather than peroxide. The system caused suppression of ovulation in four of eight monkeys, reduced uterine weights and resulted in the expected decidual endometrial changes. Cervical morphology was within normal limits and there was a slight shortening of partial thromboplastin time (which was also seen in the monkeys implanted with inert devices). Plasma levels of levonorgestrel varied between 0.1 and 0.4 ng/mL.
Overall, there was no significant difference observed between the monkeys with the levonorgestrel-releasing intrauterine system and those with the inert intrauterine system used in the study.
Reproductive and developmental toxicology
A smaller modified version of MIRENA was used for a reproductive toxicology study in rabbits. It consisted of a cylinder (diameter 2.4 mm, length 7 mm) with an inner core (5 mm) containing 12 mg levonorgestrel mixed with polydimethylsiloxane polymer, with a polydimethylsiloxane polymer membrane fitted over the core for release rate control. The release rate was calculated to be 3.5 mcg levonorgestrel per day. One system was put into each uterine horn of the pregnant rabbits.
Treatment did not have any adverse effect on litter parameters such as body weight and gross pathology, embryonic or fetal development. One rabbit in the treatment group had a hemorrhagic endometrium observed at Caesarean section. No treatment-related adverse effects were observed.
Detailed pharmacology
Levonorgestrel is a 19-nortestosterone derivative with potent progestogenic effects, but no significant estrogenic activity.
In rabbits, evidence of transformation of the endometrium was observed after subcutaneous administration of 0.01 mg levonorgestrel corresponding to 2 mcg/kg/day. Transformative effects are also histologically recognizable in the rabbit endometrium when levonorgestrel is administered orally in doses ranging from 0.03 to 0.3 mg per animal corresponding to approximately 6 to 60 mcg/kg/day.
In pregnant rats, ovariectomized within the first 4 days after conception, the subcutaneous administration of 0.002 mg levonorgestrel had a blastocyst-maintaining effect. The antiestrogenic or progestogenic activity of levonorgestrel has also been demonstrated in various test models in rats and mice. The potency of levonorgestrel is significantly higher than progesterone and about 83 times stronger than chlormadinone acetate.
Levonorgestrel does not have any significant estrogenic activity and androgenic effects are only detectable after large doses. Levonorgestrel also influences the gonadotrophic function of the anterior lobe of the pituitary gland in all experimental tests.
Like other progestogens, relative large doses of levonorgestrel lead to increases in insulin secretion in rats and dogs.