


Product Monograph - Mylan-Gemfibrozil
INDICATIONS AND CLINICAL USE
MYLAN-GEMFIBROZIL (gemfibrozil) is indicated as an adjunct to diet and other therapeutic measures for:
- 1.
Treatment of adult patients with very high serum triglyceride levels, Fredrickson classification
Type IV and V hyperlipidemias, who are at a high risk of sequelae and complications (i.e. pancreatitis) from their hyperlipidemia.
- 2. Treatment of patients with hypercholesterolemia, Type IIa and IIb mixed dyslipidemias, to regulate lipid levels (reduce serum triglycerides and LDL cholesterol levels and increase HDL cholesterol).
MYLAN-GEMFIBROZIL alone may not be adequate therapy in some patients with familial combined hyperlipidemia with Type IIb and IV hyperlipoproteinemia.
Initial therapy for hyperlipidemia should include a specific diet, weight reduction, and an exercise program; and for patients with diabetes mellitus, a good diabetic control.
CONTRAINDICATIONS
- 1. Hepatic or renal dysfunction, including primary biliary cirrhosis.
- 2. Pre-existing gallbladder disease. (See PRECAUTIONS)
- 3. Hypersensitivity to MYLAN-GEMFIBROZIL (gemfibrozil) or any of the inert ingredients.
- 4. The drug should not be used in pregnant or lactating patients.
- 5. MYLAN-GEMFIBROZIL is not indicated for the treatment of Type I hyperlipoproteinemia.
- 6.
The concomitant use of gemfibrozil with repaglinide is contraindicated (see PRECAUTIONS,
Drug Interactions).
WARNINGS
- 1.
Muscle Effects: There have been reports of severe myalgia myositis and rhabdomyolysis accompanied by markedly elevated creatinine kinase when gemfibrozil and HMG CoA reductase inhibitors were used concomitantly. (see PRECAUTIONS Drug Interactions). When rhabdomyolysis is severe the ensuing myoglobinuria can lead to acute renal failure. Therefore, HMG CoA reductase inhibitors should not be used concomitantly with gemfibrozil.
Myopathy, defined as muscle aching or muscle weakness, associated with increases in plasma creatine phopsphokinase (CPK) values to greater than 10 times the Upper Limit of Normal (ULN), should be considered in any patient with diffuse myalgias, muscle tenderness or weakness, and/or marked elevation of CPK. Patients should be advised to report promptly unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever.
The risk of myopathy and rhabdomyolosis during treatment with HMG CoA reductase inhibitors in combination with fibric acid derivatives is increased. The benefits and risks of combined therapy should be carefully considered (see PRECAUTIONS, Drug Interactions).
Rhabdomyolysis with renal dysfunction secondary to myoglobinuria have been reported with HMG-CoA reductase inhibitors. Gemfibrozil therapy should be discontinued if markedly elevated CPK levels occur or myopathy is diagnosed or suspected. Gemfibrozil should be temporarily withheld in any patient experiencing an acute or serious condition suggestive of a myopathy or having a risk factor predisposing to the development of renal failure secondary to rhabdomyolysis, e.g., sepsis; hypotension; major surgery; trauma; severe metabolic, endocrine or electrolyte disorders; or uncontrolled epilepsy.
- 2. Clofibrate: Gemfibrozil clinically, pharmacologically and chemically shows similarities with clofibrate. Physicians prescribing gemfibrozil should also be familiar with the risks and benefits of clofibrate.
- 3.
Toxicology Studies: Long-term studies with gemfibrozil have been conducted in rats and mice at one and ten times the human dose. The incidence of benign liver nodules and liver carcinomas was significantly increased in high dose male rats. The incidence of liver carcinomas was increased also in low dose males, but the increase was not statistically significant (p>0.05). In high dose female rats, there was a significant increase in the combined incidence of benign and malignant liver neoplasms. There were no statistically significant differences from controls in the incidence of liver tumors in male and female mice, but the doses tested were lower than those shown to be carcinogenic with other fibrates. Liver and testicular cell tumors were increased in male rats.
Electron microscopy studies have demonstrated a florid hepatic peroxisome proliferation following gemfibrozil administration to male rats. Such changes have not been found in the liver of patients treated with this drug.
Toxicology studies in male rats revealed a dose-related increase of benign Leydig cell tumors. Subcapsular bilateral cataracts occurred in 10% and unilateral in 6.3% of the high dose males.
- 4.
Cholelithiasis: Gemfibrozil may increase cholesterol excretion into the bile raising the potential for gallstone formation leading to cholelithiasis. If cholelithiasis is suspected,
gallbladder studies are indicated. MYLAN-GEMFIBROZIL therapy should be discontinued if gallstones are found. Cases of cholelithiasis have been reported with gemfibrozil therapy.
- 5.
General: Since a reduction of total mortality has not been demonstrated, MYLAN-
GEMFIBROZIL should be administered only in those patients described in the INDICATIONS section. If a significant serum lipid response is not obtained in 3 months, MYLAN-GEMFIBROZIL should be discontinued.
If MYLAN-GEMFIBROZIL is chosen for treatment, the prescribing physician should discuss the proposed therapy and inform the patient of the expected benefits and potential risks which may be associated with long-term administration. (See PRECAUTIONS)
- 6. Use in Children: Safety and efficacy in children have not been established.
- 7.
Use in Pregnancy: Strict birth control procedures must be exercised by women of childbearing potential. If pregnancy occurs despite birth control procedures, MYLAN-GEMFIBROZIL should be discontinued.
Women who are planning pregnancy should discontinue MYLAN-GEMFIBROZIL several months prior to conception.
- 8. Nursing mother: Because of the potential for tumorigenicity shown for gemfibrozil in rats, a decision should be made whether to discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
PRECAUTIONS
- 1. Initial Therapy: Before instituting MYLAN-GEMFIBROZIL (gemfibrozil) therapy, attempts should be made to control serum lipids and lipoproteins with appropriate diet, exercise, weight loss in obese patients, and control of diabetes mellitus.
- 2. Long-term Therapy: Because long-term administration of MYLAN-GEMFIBROZIL is recommended, pretreatment clinical chemistry studies should be performed to ensure that the patient has elevated serum lipid or low HDL cholesterol levels. Periodic determinations of serum lipids and lipoproteins should be done during MYLAN-GEMFIBROZIL administration, including measurement of LDL-cholesterol/HDL-cholesterol ratio, particularly in Type IV hyperlipoproteinemic patients.
- 3. Impairment of Fertility: Administration of approximately three and ten times the human dose to male rats for 10 weeks resulted in a dose-related decrease of fertility. Subsequent studies demonstrated that this effect was reversed after a drug-free period of about 8 weeks, and it was not transmitted to their offspring.
- 4. Hematologic Changes: Mild hemoglobin, hematocrit and white blood cells (WBC) decrease have been observed occasionally following initiation of gemfibrozil therapy. The levels then stabilize during long-term administration. Rarely, severe anemia, leukopenia, thrombocytopenia, eosinophilia and bone marrow hypoplasia have been reported. Therefore, periodic blood count determinations are recommended during the first 12 months of MYLAN-GEMFIBROZIL administration.
- 5. Liver Function: Abnormal liver function tests have been observed occasionally during gemfibrozil administration, including elevations of AST, ALT, LDH, alkaline phosphatase, creatine kinase, and bilirubin. These are usually reversible when gemfibrozil is discontinued. Therefore, periodic liver function studies are recommended and MYLAN-GEMFIBROZIL therapy should be terminated if abnormalities persist.
- 6.
Hepatobiliary Disease: In patients with a past history of jaundice or hepatic disorder, MYLAN-
GEMFIBROZIL should be used with caution.
- 7. Cardiac Arrhythmias: Although no clinically significant abnormalities occurred that could be attributed to gemfibrozil, the possibility exists that such abnormalities may occur.
- 8.
Drug Interactions: When gemfibrozil and lovastatin were used concomitantly there have been reports of severe myalgia, myositis and rhabdomyolysis accompanied by markedly elevated CK. When rhabdomyolysis is severe, the ensuing myoglobinuria can lead to acute renal failure. Therefore, lovastatin should not be used concomitantly with MYLAN-GEMFIBROZIL.
Anticoagulants: Caution should be exercised when anticoagulants are given in conjunction with MYLAN-GEMFIBROZIL. The dosage of the anticoagulant should be reduced to maintain the prothrombin time at the desired level to prevent bleeding complications. Frequent prothrombin determinations are advisable until it has been definitely determined that the prothrombin level has stabilized.
Bile Acid-Binding Resins: Reduced bioavailability of MYLAN-GEMFIBROZIL may result when given simultaneously with resin-granule drugs such as colestipol. Administration of the drugs two hours or more apart is recommended.
HMG-CoA reductase inhibitors: There have been reports of severe myalgia, myositis and rhabdomyolysis accompanied by markedly elevated creatine kinase (CK) when gemfibrozil and HMG-CoA reductase inhibitors, were used concomitantly. When rhabdomyolysis is severe the ensuing myoglobinuria can lead to acute renal failure. Therefore, HMG-CoA reductase inhibitors should not be used concomitantly with MYLAN-GEMFIBROZIL (see WARNINGS, Muscle Effects).
Repaglinide: Serious cases of hypoglycemia have been reported following the concomitant use of repaglinide and gemfibrozil. This is likely due to inhibition of CYP 2C8 by gemfibrozil as evidenced by decreases in blood glucose that were proportional to the dose of gemfibrozil. In healthy volunteers, the levels of repaglinide were significantly increased when co-
administered with gemfibrozil. The averaged area under the curve (AUC) was increased 8- fold (range 6- to 15 fold) and the half-life increased 3 fold. When itraconazole, an inhibitor of CYP 3A4, was also given with gemfibrozil and repaglinide, even greater effects were observed: AUC for repaglinide was increased 19-fold and the half-life increased from 1.3 to 6 hours. (see CONTRAINDICATIONS).
CYP2C8 inhibition by gemfibrozil can affect the metabolism of several major cardiovascular drugs such as amiodarone, verapamil, warfarin but also other drugs such as tolbutamide.
Gemfibrozil is also known to potently inhibit CYP2C9 activity. Therefore, CYP2C9 inhibition by gemfibrozil can affect the metabolism of several major cardiovascular drugs such as carvedilol and losartan but also other drugs such as phenytoin and diazepam (see CLINICAL PHARMACOLOGY AND PHARMACOKINETICS).
ADVERSE REACTIONS
(i) Pre-Marketing Studies:
Gemfibrozil has been carefully evaluated in over 3,000 patients having received the drug in monitored clinical studies prior to marketing. Symptoms reported during the controlled phase in studies of 805 subjects were considered for safety. The symptoms listed in Table 1 are those which occurred in at least 5 patients and all skin reactions whatever their incidence. The principal symptoms for which incidence was greater with gemfibrozil than with placebo involved the gastrointestinal system. Nausea and vomiting, and abdominal and epigastric pain occurred more often in the gemfibrozil group than in the placebo group. However, the incidence was low: nausea, 4.3% with gemfibrozil versus 3.8% with placebo; vomiting, 2.3% versus 0.8%; abdominal pain, 6.4% versus 4.2%; and epigastric pain, 3.4% versus 1.7%.
Table 1. Incidence of Symptoms Reported in Controlled Pre-Marketing Studies
Symptom Gemfibrozil
(n = 529)
Placebo
(n = 236) BODY AS A WHOLE
Dizziness 2.8% 4.2% Chest pain 2.1% 1.7% Fatigue 0.9% 0.4% INTEGUMENTARY
Rash 2.5% 1.3% Pruritis 0.8% 1.3% Dermatitis 0.6% 0.4% Urticaria 0.2% 0.0% MUSCULOSKELETAL
Pain in extremities 1.5% 1.7% GASTROINTESTINAL
Abdominal pain 6.4% 4.2% Diarrhea 4.9% 5.1% Nausea 4.3% 3.8% Epigastric pain 3.4% 1.7% Vomiting 2.3% 0.8% Flatulence 1.5% 2.1% ENDOCRINE
Gout 0.9% 0.8% CENTRAL NERVOUS SYSTEM
Headache 2.3% 4.2% Paresthesia 0.9% 0.4% SPECIAL SENSES
Blurred vision 1.1% 0.8%
Number of Patients Withdrawn for
Clinical Symptoms
1.3% 1.3%
Additional adverse reactions that have been reported, where a causal relationship to treatment with gemfibrozil is probable, are:
Hepatobiliary disorders: Cholestatic jaundice
Gastrointestinal disorders: Pancreatitis
Nervous System disorders: Dizziness, somnolence, paresthesia, peripheral neuritis, headache Psychiatric disorders: Decreased libido, depression
Eye disorder: Blurred vision
Reproductive system and Breast disorders: Impotence
Musculoskeletal and connective tissue disorders: Arthralgia, synovitis, myalgia, myopathy, myasthenia, painful extremities, rhabdomyolysis (See WARNINGS: Drug Interactions)
Skin and subcutaneous tissue disorders: Exfoliative dermatitis, rash, dermatitis, pruritus, angioedema, urticaria, photosensitivity Respiratory, thoracic and mediastinal disorders: Laryngeal edema
Blood and lymphatic system disorders: Severe anemia, leukopenia, thrombocytopenia, eosinophilia, bone marrow hypoplasia (see PRECAUTIONS - Hematologic Changes)
Additional adverse reactions that have been reported included photosensitivity, alopecia, cholecystitis and cholelithiasis (see WARNINGS).
(ii) Post-Marketing Study (Helsinki Heart Study):
The long-term safety of gemfibrozil was established in the Helsinki Heart Study, a 5-year primary prevention Phase IV clinical trial. In the double-blind phase of the Helsinki Heart Study, 2,046 patients received gemfibrozil for up to 5 years. Table 2 lists the most frequently reported adverse events and includes those occurring in at least 1% of all subjects treated with gemfibrozil. Dyspepsia (19.6% versus 11.9%), abdominal pain (9.8% versus 5.6%), acute appendicitis (1.2% versus 0.6%) and atrial fibrillation (0.7% versus 0.1%) occurred more often in the gemfibrozil group than the placebo group, while all other adverse events were similar in frequency between the two groups.
Table 2. Incidence of Adverse Events in Controlled Phase of Helsinki Heart Study
Adverse Event
Gemfibrozil
(n = 2046)
Placebo (n = 2035)
BODY AS A WHOLE
Fatigue 3.8% 3.5% Headache 1.2% 1.1% DIGESTIVE SYSTEM
Dyspepsia 19.6% 11.9% Abdominal pain 9.8% 5.6% Diarrhea 7.2% 6.5% Flatulence 5.3% 5.2% Nausea and/or vomiting 2.5% 2.1% Constipation 1.4% 1.3% Acute appendicitis 1.2% 0.6% NERVOUS SYSTEM
Vertigo 1.5% 1.3% SKIN AND APPENDAGES
Eczema 1.9% 1.2% Rash
1.7% 1.3%
Number of Patients Withdrawn
Due to Adverse Events
10.4% 7.3%
REPORTING SUSPECTED SIDE EFFECTS
You can report any suspected adverse reactions associated with the use of health products to the Canada Vigilance Program by one of the following 3 ways:
- Report online at www.healthcanada.gc.ca/medeffect
- Call toll-free at 1-866-234-2345
Complete a Canada Vigilance Reporting Form and:
-Fax toll-free to 1-866-678-6789, or
-Mail to: Canada Vigilance Program
Health Canada
Postal Locator 0701D
Ottawa, ON K1A 0K9
Postage paid labels, Canada Vigilance Reporting Form and the adverse reaction reporting guidelines are available on the MedEffectTM Canada Web site at www.healthcanada.gc.ca/medeffect.
NOTE: Should you require information related to the management of side effects, contact your health professional. The Canada Vigilance Program does not provide medical advice.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Overdosage has been reported with gemfibrozil. Symptoms reported with overdosage were abdominal cramps, abnormal liver function tests, diarrhea, increased CPK, joint and muscle pain, nausea and vomiting. In one case of accidental overdosage, where a child ingested 9 g of gemfibrozil, non-specific symptoms of nausea and vomiting were reported. The patient fully recovered.
Symptomatic supportive measures should be taken should overdosage occur.
| For management of a suspected drug overdose, contact your regional Poison Control Centre | ||
| Immediately. |
DOSAGE AND ADMINISTRATION
The recommended dose for adults is 1200 mg administered in two divided doses (two 300 mg capsules or one 600 mg tablet twice a day) 30 minutes before the morning and evening meal. The maximum recommended daily dose is 1500 mg.
PHARMACEUTICAL INFORMATION
Drug Substance
PROPER NAME: Gemfibrozil
CHEMICAL NAME: 5-(2,5-dimethylphenoxy)-2,2-dimethylpentanoic acid
STRUCTURAL FORMULA:
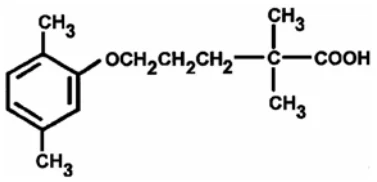
MOLECULAR FORMULA: C15H22O3
MOLECULAR WEIGHT: 250.35
DESCRIPTION: Gemfibrozil is a nonhalogenated phenoxypentanoic acid. It is a white, waxy powder which is stable under ordinary conditions.
MELTING RANGE: The melting point is 58-61oC.
Solubility: Practically insoluble in water, soluble in alcohol, in methanol, and in chloroform.
pH: about 4.0 for a 0.2% solution in a 1:1 mixture of water and methanol.
pKa: 6.2 for a 0.2% solution in a 1:1 mixture of water and methanol.
Composition:
300 mg Capsules: non-medicinal ingredients; Corn Starch, FD&C Blue #1, FD&C Red #3, Gelatin, Polysorbate 80, Silicon Dioxide, Titanium Dioxide and the printing ink contains Black Iron Oxide, Shellac, Propylene Glycol, Ammonium Hydroxide, Potassium Hydroxide.
600 mg Tablets: non-medicinal ingredients; Polysorbate, Microcrystalline Cellulose, Hydroxypropyl Cellulose, Croscarmellose Sodium, Colloidal Silicon Dioxide, Calcium Stearate,
Titanium Dioxide, Polydextrose, Hydroxypropyl Methylcellulose, Pregelatinized Starch, Triethyl Citrate and Polyethylene Glycol.
Stability and Storage
Recommendations: MYLAN-GEMFIBROZIL (gemfibrozil) should be stored between 15oC to 30oC. Protect from humidity.
AVAILABILITY OF DOSAGE FORMS
MYLAN-GEMFIBROZIL (gemfibrozil) preparations are formulated as 300 mg capsules and 600mg tablets.
MYLAN-GEMFIBROZIL 300 mg capsules is available in size O capsule with white and maroon colour and print in black with "G" on cap and "G300" on body. Each capsule contains 300 mg gemfibrozil and is available in bottles of 100 capsules.
MYLAN-GEMFIBROZIL 600 mg tablets is available in white, oval, film coated tablet with “G600" on one side and plain on the other. Each tablet contains 600 mg gemfibrozil and is available in bottles of 100 tablets.
PHARMACOLOGY
Pharmacokinetics:
Two separate comparative bioavailability studies were performed to compare the rate and extent of absorption of MYLAN-GEMFIBROZIL capsules 300 mg (X2) and MYLAN-GEMFIBROZIL tablets 600 mg (X1) against a Canadian Reference Brand, Lopid® (gemfibrozil) capsules 300 mg (X2) and Lopid® (gemfibrozil) tablets 600 mg (X1) respectively. The results of the bioavailability study are presented below:
Gemfibrozil 300 mg Capsules (2 X 300 mg):
MEAN PHARMACOKINETIC DATA
Gemfibrozil
(2 x 300 mg)
From measured data
Geometric Mean
Arithmetic Mean (CV %)
| Parameter | Test* Gen-Gemfibrozil** | Reference† Lopid® | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (μg.hr/mL) | 81.37 82.24 (18.5%) | 80.40 82.44 (31.8%) | 101.3 | 96.8% - 106.0% |
| AUCI (μg.hr/mL) | 83.01 83.79 (17.4%) | 81.86 83.86 (30.8%) | 101.2 | 96.8% - 105.9% |
| Cmax (μg/mL) | 34.92 35.59 (54.4%) | 29.49 30.42 (84.0%) | 118.4 | 109.0% - 128.6% |
| Tmax (hr)* | 1.47 (59.9%) | 1.90 (41.1%) | ||
| T1/2 (hr)* | 1.10 (16.4%) | 1.12 (13.4%) |
* The Tmax and T1/2 parameters are expressed as the arithmetic means (CV%) † Lopid® (Gemfibrozil) Caps, 300 mg Manufactured by Parke Davis, Canada **Gen-Gemfibrozil – currently known as Mylan-Gemfibrozil.
Gemfibrozil 600 mg tablets (1 X 600 mg):
MEAN PHARMACOKINETIC DATA
Gemfibrozil
(1 x 600 mg)
From measured data
Geometric Mean
Arithmetic Mean (CV %)
| Parameter | Test* Gen- Gemfibrozil** | Reference† Lopid® | % Ratio of Geometric Means | 90% Confidence Interval |
| AUCT (μg.hr/mL) | 59.92 61.99 (26.9%) | 55.71 57.83 (29.5%) | 107.6 | 101.0% - 114.5% |
| AUCI (μg.hr/mL) | 58.16 60.86 (25.6%) | 54.87 57.25 (29.1%) | 106.0 | 99.4% - 113.0% |
| Cmax (μg/mL) | 21.00 22.02 (29.9%) | 17.22 18.10 (33.9%) | 122.0 | 103.4% - 143.9% |
| Tmax (hr)* | 1.53 (52.0%) | 1.72 (46.9%) | ||
| T1/2 (hr)* | 1.69 (64.1%) | 2.21 (70.8%) |
* The Tmax and T1/2 parameters are expressed as the arithmetic means (CV%)
† Lopid® (Gemfibrozil) Tabs., 600 mg Manufactured by Warner Lambert a Div. of Parke Davis, Canada. **Gen-Gemfibrozil – currently known as Mylan-Gemfibrozil.
The hypolipidemic activity of gemfibrozil has been demonstrated in laboratory animals, with most of the work done with rats. Studies in normal rats showed that gemfibrozil was 15 times more active than clofibrate in reducing triglycerides at doses as low as 7.5 mg/kg over seven days. However, gemfibrozil had no effect on total plasma cholesterol at any dose tested because it increased the HDL fraction by 50% to 70%. Oral doses of 25 mg/kg/day administered to hyperlipidemic rats caused a 75% reduction in the triglyceride level, while clofibrate at four times that dose had no significant effect.
In cholesterol-fed rats with abnormally low HDL cholesterol levels, oral administration of gemfibrozil at doses of 12.5 to 50 mg/kg/day produced elevations in the HDL fraction of 200% to 600%. When lipids were extracted from the liver and measured, it was found that gemfibrozil had caused a dramatic reduction in the liver cholesterol content below the control level at both one and two weeks, suggesting enhanced removal of previously deposited cholesterol.
The mechanism by which these actions occur has not been firmly established. Additional studies in rats suggest that gemfibrozil inhibits the incorporation of long-chain fatty acids into newly formed triglycerides and inhibits basal adipose tissue lipolysis. Gemfibrozil also inhibits the production and increases the turnover rate of the beta-apolipoprotein moiety of VLDL, the resulting decrease in VLDL production providing the basis for the drug's ability to reduce lipid levels.
Gemfibrozil has no significant cardiovascular or central nervous system activity.
CLINICAL PHARMACOLOGY AND PHARMACOKINETICS
Gemfibrozil is well absorbed from the gastrointestinal tract following oral administration to laboratory animals and humans.
In animals, gemfibrozil is excreted in both urine and feces. In rats and dogs, the major route of excretion is fecal, accounting for 47% and 62% of a given dose in the two species, respectively. In monkeys, urinary excretion predominates, 62% of an administered dose being excreted by that route in four days; fecal excretion accounted for only 2% of the dose.
In human subjects, approximately 70% of a given dose is excreted in the urine, primarily as the glucuronide conjugate, with less than 2% excreted as unchanged gemfibrozil; 6% of the dose is accounted for in the feces. Peak plasma levels occur in one to two hours following single doses. The mean half-life was approximately 1.5 hours following single doses and 1.3 hours following multiple doses. Plasma levels appear proportional to dose and do not demonstrate accumulation across time following multiple doses.
Three metabolic pathways have been identified. The first metabolic pathway is that of conjugation of gemfibrozil and its metabolites. The second, and presumably the principal route, involves hydroxylation of the meta-methyl group of gemfibrozil, yielding a benzyl alcohol (Metabolite II) that undergoes rapid oxidation to a benzoic acid metabolite (Metabolite III, the major metabolite). The third pathway involves hydroxylation of the aromatic ring to a phenol (Metabolite I) which is further converted to a compound (Metabolite IV) with no intact carboxylic acid function, but which is phenolic in nature.
CYP2C8 inhibition by gemfibrozil can affect the metabolism of several major cardiovascular drugs such as amiodarone, verapamil, warfarin but also other drugs such as tolbutamide.
Gemfibrozil is also known to potently inhibit CYP2C9 activity. Therefore, CYP2C9 inhibition by gemfibrozil can affect the metabolism of several major cardiovascular drugs such as carvedilol and losartan but also other drugs such as phenytoin and diazepam (see PRECAUTIONS - Drug Interactions).
Gemfibrozil is completely absorbed after oral administration, reaching peak plasma concentrations one to two hours after dosing. Gemfibrozil pharmacokinetics are affected by the timing of meals relative to time of dosing. In one study, both the rate and extent of
absorption of the drug were significantly increased when administered 0.5 hour before meals. Average Area Under the Curve (AUC) was reduced by 14 to 44% when gemfibrozil was administered after meals compared to 0.5 hour before meals. In a subsequent study, rate of absorption of gemfibrozil was maximum when administered 0.5 hour before meals with the Cmax 50-60% greater than when given either with meals or fasting. In this study, there were no significant effects on AUC of timing of dose relative to meals.
Gemfibrozil is highly bound to plasma proteins and there is potential for displacement interactions with other drugs.
CLINICAL EXPERIENCE
Gemfibrozil versus Placebo
In a large multicentre trial of 427 patients, 108 patients having Fredrickson type IIa, 107 patients, type IIb and 212 patients, type IV hyperlipidemia, the effect of gemfibrozil on lipoprotein fractions was compared to that of placebo. In the initial, controlled phase of the trial, patients were randomly assigned to one of two treatment groups; subjects in group A received placebo for 6 weeks, then received increasing doses of gemfibrozil, 800 mg/day, 1200 mg/day and 1600 mg/day each dose for 6 weeks; those in group B received placebo for the entire period. Following this, the subjects entered a single-blind period in which subjects in group B received the rising doses of gemfibrozil, and those in group A, after 6 weeks on placebo, entered a long-term, open label phase. The following lipid measurements were made: total cholesterol, triglycerides, very low density lipoproteins (VLDL), low density lipoproteins (LDL), and high density lipoproteins (HDL).
Total Cholesterol: In patients with type IIa and type IIb hyperlipoproteinemia, gemfibrozil therapy resulted in a statistically significant decrease of total cholesterol with all doses, except the 1200 mg dose among the type IIa subjects. In patients with type IV hyperlipidemia, gemfibrozil had no significant effect on total cholesterol.
Triglycerides: In all three groups of patients, gemfibrozil therapy resulted in a significant decrease of serum triglyceride levels. At the 1200 mg daily dose, triglycerides were decreased by 44% in type IIa patients, by 45% in the type IIb group, and by 40% in type IV patients.
HDL-Cholesterol: In all three hyperlipoproteinemia types studied, gemfibrozil therapy was associated with a significant elevation of the high density lipoprotein fraction. At the 1200 mg daily dose in type IIa, IIb and type IV patients, the increase of HDL-cholesterol was 24.6%, 19.5% and 17.4%, respectively.
Measurement of HDL-cholesterol to total cholesterol ratio is often employed as a useful parameter in blood lipid profile. This ratio showed a significant increase during gemfibrozil therapy, amounting to 33%, 34% and 23%, respectively, in the three groups studied.
Following the controlled phase of the multicentre trial, 349 subjects entered a long-term open treatment phase with gemfibrozil. Total cholesterol, triglycerides and total LDL-cholesterol levels consistently remained below the baseline placebo values throughout the long-term trial. HDL-cholesterol and the HDL-cholesterol to total cholesterol ratio both consistently remained above the placebo baseline values during the long-term trial. By the end of 12 lunar months of treatment, the improvement in lipid values had increased for nearly every parameter. The greatest changes during the long-term treatment were observed in total cholesterol, LDL-cholesterol, total LDL-cholesterol, and HDL-cholesterol to total cholesterol ratio. These results indicate that the improvement achieved during the control period was maintained or increased during the long-term trial.
Gemfibrozil versus Clofibrate
The lipid regulating effect of gemfibrozil was also studied against clofibrate. In a study of 32 patients with type IIa, IIb or type IV hyperlipidemia, 17 patients were treated with gemfibrozil, 1200 mg per day, and 15 patients with clofibrate, 2000 mg per day, for 18 weeks. The two drugs had similar effects on total plasma cholesterol, triglycerides and LDL-cholesterol levels, but gemfibrozil had significantly greater effect in elevating HDL-cholesterol and HDL/total cholesterol ratios. The mean percent increases in HDL-cholesterol levels were 22.4% with gemfibrozil and 8.6% with clofibrate, while the HDL/total cholesterol ratio increased 43.0% with gemfibrozil and 25.9% with clofibrate.
Primary-Prevention Trial (Helsinki Heart Study)
The Helsinki Heart Study investigated the effect of gemfibrozil on the incidence of coronary heart disease (CHD) in a randomized, double-blind, five-year trial in middle-aged men (40 to 55 years of age) who were free of coronary heart symptoms on entry, but were at a high risk because of abnormal levels of blood lipids (i.e. non-HDL-cholesterol > 200 mg/dl). The study was aimed at testing the hypothesis that reducing serum total cholesterol and LDL-cholesterol, and increasing HDL-cholesterol with gemfibrozil would reduce the incidence of cardiac disease. One group of men (2,046) received 1200 mg (600 mg b.i.d.) of gemfibrozil per day and another group (2,035) received placebo. In terms of Fredrickson types, the subjects entered into the study were distributed as follows:
Treatment Group Fredrickson Type Total
Number
Type IIa Type IIb Type IV Type V
LOPID 1293 570 182 1 2046 Placebo 1297 561 177 0 2035
Serum lipids (i.e. total triglycerides, total cholesterol, LDL-cholesterol and HDL cholesterol) were measured periodically during the study. Efficacy of treatment was determined by comparing the incidence of cardiovascular endpoints (i.e. fatal and nonfatal myocardial infarction, sudden and unwitnessed cardiac death) on an intent-to-treat basis.
Gemfibrozil caused a marked change in the serum lipid levels of patients. The lipid changes occurred rapidly, being noted during the first 3-months of treatment and persisted over the 5-year treatment period. The percent changes in serum lipid levels of the gemfibrozil group by Fredrickson type averaged across the 5-year study period relative to baseline are shown in the following table:
% Change From Baseline in Gemfibrozil Group
Over 5-Year Period
Serum Lipid Parameter Type IIa Type IIb Type IV All Subjects1
(n = 1293) (n = 570) (n = 182) (2046)
Triglycerides -26.3% -44.3% -49.9% -37.3%
Total Cholesterol -9.2% -8.6% -5.0% -8.7%
LDL-Cholesterol -11.4% -4.1% +4.8% -8.2%
HDL-Cholesterol +8.5% +11.7% +9.6% +9.0%
Non-HDL-Cholesterol -13.5% -12.4% -7.8% -12.5%
1 One subject was a Fredrickson Type V.
In the gemfibrozil group, decreases of 37%, 9%, 8% and 12.5% occurred in triglycerides, total cholesterol, LDL-cholesterol, and non-HDL-cholesterol respectively, and HDL-cholesterol increased by 9%. In contrast, changes in serum lipid levels of the placebo group over the 5-years relative to baseline were small and inconsistent. Statistical analyses revealed a significant difference between the gemfibrozil group and placebo group for every lipid parameter at each year and across all years (p<0.001). Statistical differences were also evident for all lipid parameters between treatment groups by Fredrickson type at each year and across all years (p<0.001), with the exception of LDL cholesterol in Type IV subjects.
The annual frequency of cardiovascular endpoints over the 5-year study period is shown in the table below:
Year Treatment and
Endpoint 1 2 3 4 5
Total Number (Rate/1000) Number of Subjects
Gemfibrozil (n=2046):
Nonfatal MI1 12 13 7 6 6 45 (22.0)2 Fatal MI 0 0 4 2 0 6 (2.9) Sudden CD1 1 0 1 2 1 5 (2.4) Unwitnessed CD 0 0 0 0 0 0 (0.0) Total
14 13 12 10 7 56 (27.4)
Placebo (n=2035):
Nonfatal MI 11 11 13 18 18 71 (34.9) Fatal MI 2 3 1 0 2 8 (3.9) Sudden CD 0 1 2 1 0 4 (2.0) Unwitnessed CD 0 0 0 0 1 1 (0.5) Total
13 15 16 19 21 84 (41.3)
1 MI = myocardial infarction; CD = cardiac death.
2 Three subjects in the gemfibrozil group and 6 in the placebo group died later after surviving previous MI.
The effect of gemfibrozil on the incidence of cardiovascular endpoints was first established during the third year and became more prominent over Years 4 and 5 of the study. Analyses of the incidence of cardiovascular endpoints on an intent-to-treat basis revealed that over the 5-year study period, the gemfibrozil group experienced a 34% reduction in the overall incidence of CHD compared to placebo (27.4 per 1,000 in the gemfibrozil group versus 41.3 per 1,000 in the placebo group); in Years 3 to 5 of the study, the reduction in CHD was greater than 50%. There was an overall 37% reduction in nonfatal myocardial infarction (22.0 per 1,000 in the gemfibrozil group versus 34.9 per 1,000 in the placebo group) and a 26% reduction in cardiac deaths (14 deaths in total or 6.8 per 1,000 in the gemfibrozil group versus 19 deaths in total or 9.3 per 1,000 in the placebo group). The greatest reduction in incidence of serious cardiac events occurred in Type IIb patients.
The data from the Helsinki Heart Study suggested that the correlation between changes in lipids (increasing HDL-cholesterol 8.0% and decreasing LDL-cholesterol 7.3%) and reducing CHD incidence should have brought reductions of 23% and 15% respectively in CHD incidence. When the joint effects of HDL-cholesterol (+8.0%) and LDL-cholesterol (-7.3%) were taken into consideration simultaneously, the predicted reduction in CHD incidence was 28% in the gemfibrozil group.
There was no difference between the groups in the total death rate (all causes) over the 5-year study period.
LITHOGENICITY
Pre-Marketing Study
The effect of gemfibrozil on gallstone formation was studied both in normal volunteers and in hyperlipidemic subjects.
In 10 healthy male volunteers, gemfibrozil and clofibrate were studied according to a cross-over design. Changes in concentrations of bile phospholipid, cholesterol and bile acid were measured and a lithogenic index was calculated. While clofibrate showed a significant potential for lithogenicity, the gemfibrozil results were not significantly different from baseline.
Since the above study suggested a low lithogenic potential for gemfibrozil, further studies were carried out in a group of over 200 patients with dyslipoproteinemias who received gemfibrozil for 2 years or more and who had cholecystograms immediately prior to receiving the drug and at 1-year and 2-year intervals. During the period of study, 5 patients developed radiological evidence of cholelithiasis, an annual incidence of 1.21%. This figure is not different from the incidence of newly observed gallstones in the general population. Based on these data, gemfibrozil does not seem to have a significant lithogenic potential.
Post-Marketing Study
A gallstone prevalence substudy of 450 Helsinki Heart Study participants showed a trend toward a greater prevalence of gallstones during the study within the gemfibrozil treatment group (7.5% versus 4.9% in the placebo group). In addition, more patients underwent surgical operations (cholecystectomy, cholecystotomy, appendectomy) while on gemfibrozil therapy.
TOXICOLOGY
Acute Toxicity
LD50 (mg/kg)
Species Sex Oral
I.P.
Mice
M&F
3162
380
Rat
M&F
4786
360
The effects of single dose gemfibrozil administration to mice and rats showed that the toxicity of the drug was low. Clinical signs of intolerance were similar for both species and included incoordination, depression, flaccid prostration and dyspnea. The only microscopic change was hepatocellular enlargement.
Two beagle dogs were given increasing daily doses of gemfibrozil over a 49-day period. At a dose level of 500 mg/kg, signs of intolerance, such as occasional vomiting and decreased activity, were observed. As the dose level was increased, these symptoms became more frequent and prominent, and finally anorexia, weight loss, and incoordination occurred. One dog died
following a dose of 875 mg/kg. At autopsy, congestion and focal mucosal hemorrhage were the only prominent gross findings.
Chronic Toxicity
Gemfibrozil was administered to rats and dogs for 12 months. The rats were given daily doses of 30, 150 and 300 mg/kg and the dogs received 25, 150 and 300 mg/kg - the top dose level representing about 15 times the average effective daily human dose.
The 12-month study in rats showed only a dose-related suppression of weight gain. There were fluctuations in hematological and blood biochemical values, but they were neither consistent nor clearly dose-related. Microscopic findings revealed that abnormalities were confined to the liver and consisted primarily of an abundance of microbodies and a marked increase in smooth endoplasmic reticulum in the cell cytoplasm. Such changes are thought to be adaptive rather than degenerative.
In the one-year dog study, gemfibrozil was clinically well-tolerated. Gross autopsy disclosed no drug-related abnormalities. Histopathologic findings revealed that the increase in microbodies, as observed in rats, was not a prominent feature in the hepatocytes of the dogs.
Tumorigenicity Studies
Gemfibrozil was given as a dietary admixture at daily doses of 30 and 300 mg/kg to two groups of 50 rats of each sex for 2 years, and another group of 50 rats served as untreated controls. Histologically, the incidence of benign liver nodules and liver carcinomas was significantly increased in high dose male rats. The incidence of liver carcinomas increased also in low dose males, but this increase was not statistically significant (p>0.05). In high dose female rats, there was a significant increase in the combined incidence of benign and malignant liver neoplasms. Electron microscopy studies have demonstrated a florid hepatic peroxisome proliferation following gemfibrozil administration to male rats. Similar changes have not been found in the human liver based on biopsy material.
An 18 month study was conducted in mice. Gemfibrozil at daily doses of 30 and 300 mg/kg was given as a dietary admixture to two groups of 72 mice per sex, and an additional group of 72 mice of each sex served as untreated controls. A number of animals died during the course of the study; these deaths were equally distributed among the different groups and no significant differences in mortality rates were found. There were no significant clinical or ophthalmic changes attributable to gemfibrozil. A slight to moderate weight gain suppression occurred in treated animals in a dose related fashion. No histopathological changes were attributed to gemfibrozil except for slight hypertrophy and increased eosinophilia of hepatocytes in the centrolobular area in high dose males. Tumors occurred randomly and there were no statistically significant differences from controls in the incidence of liver tumors in treated male and female mice, but the doses tested were lower than those shown to be carcinogenic with other fibrates.
A comparative carcinogenicity study was also done in rats comparing three drugs in this class: fenofibrate (10 and 60 mg/kg; 0.3 and 1.6 times the human dose), clofibrate (400 mg/kg; 1.6
times the human dose), and gemfibrozil (250 mg/kg; 1.7 times the human dose). Pancreatic acinar adenomas were increased in males and females on fenofibrate; hepatocellular carcinoma and pancreatic acinar adenomas were increased in males and hepatic neoplastic nodules in females treated with clofibrate; hepatic neoplastic nodules were increased in males and females treated with gemfibrozil while testicular interstitial cell tumors were increased in males on all three drugs.
Reproduction and Teratology Studies
Gemfibrozil was administered in oral doses of approximately 95 and 325 mg/kg/day to male and female rats for 61 and 15 days respectively before mating. Dosing was continued through pregnancy and weaning of offspring. Gemfibrozil produced a dose-related suppression of fertility but had no effect on length of gestation, duration of parturition, litter size, or embryonic or fetal wastage. Treated males were responsible for the reduced fertility rate, probably because of the marked suppression of weight gain they experienced.
Gemfibrozil was administered to pregnant rats and rabbits during the critical period of organogenesis. Rats were given gemfibrozil in the diet in doses of 81 and 281 mg/kg on days 6 through 15 of gestation. Artificially inseminated rabbits were given gemfibrozil by gavage at 60 and 200 mg/kg on days 6 through 18 of gestation. Examination of fetuses removed from treated rats and rabbits one day before expected parturition disclosed no significant effects on either litter or fetal characteristics, nor were significant malformations found among almost 400 offspring from 36 litters of treated rats or 100 fetuses from 22 litters of treated rabbits.
Mutagenicity
Gemfibrozil was studied under standard test conditions for point mutations by the Ames test. Five strains of Salmonella typhimurium and 3 concentrations of gemfibrozil, (100, 500 and 2500 mcg/plate), with and without metabolic activation, were tested. The resultant number of revertant colonies, in the presence or absence of metabolic activation, was not increased over control at any concentration tested in the five strains. It was concluded that gemfibrozil showed no mutagenic potential in the five strains of Salmonella tested.
BIBLIOGRAPHY
Fodor JG, Frohlich JJ, Genest JJG Jr, et al. Recommendations for the Management and Treatment of Dyslipidemia. Report of the Working Group on Hypercholesterolemia and Other Dyslipidemias. Can Med Assoc J. May 16, 2000; 162 (10): 1441-1447.
Eisalo A, Manninen V. Gemfibrozil and clofibrate in the treatment of hyperlipidemias: A comparative trial. Proc Roy Soc Med 1976; 69(Suppl 2):44-46.
Fenderson R, et al. Effect of gemfibrozil on serum lipids in man. Angiology 1982; 33(9):581-593.
Forland S, Feng Y, Cutler R. Apparent reduced absorption of gemfibrozil when given with colestipol. J Clin Pharmacol 1990; 30(1):29-32.
Frick M, Elo O, Haapa K, et al. Helsinki Heart Study: Primary-prevention trial with gemfibrozil in middle-aged men with dyslipidemia. Safety of treatment, changes in risk factors, and incidence of coronary heart disease". N Engl J Med 1987; 317(20):1237-1245.
Garg A, Grundy S. Gemfibrozil alone and in combination with lovastatin for treatment of hypertriglyceridemia in NIDDM. Diabetes 1989; 38:364-372.
Goldstein MR. Myopathy and rhaddomyolysis with lovastatin taken with gemfibrozil. JAMA 1990;264(23):2991.
Gotto A. Symposium on high-density lipoproteins and coronary artery disease: Effects of diet, exercise, and pharmacologic intervention. Am J Cardiol 1983; 52(4):1B-43B.
Heinonen O, Huttunen J, Manninen V, et al. The Helsinki Heart Study: coronary heart disease incidence during an extended follow-up. J Int Med 1994; 235:41-49.
Hodges R, Marcus E. Safety of gemfibrozil (Lopid) in clinical use. Research and Clinical Forum 1982; 4(2):35-40.
Huttunen J, Heinonen O, Manninen V, et al. The Helsinki Heart Study: an 8.5 year safety and mortality follow-up. J Int Med 1994; 235:31-39.
Kashyap M. Basic considerations in the reversal of atherosclerosis: Significance of high-density lipoprotein in stimulating reverse cholesterol transport. Am J Cardiol 1989; 63 :56H-59H.
Kaukola S, Manninen V, Malkonen M, et al. Gemfibrozil in the treatment of dyslipidemias in middle-aged male survivors of myocardial infarction. Acta Med Scand 1981; 209:69-73.
Konttinen A, Kuisma I, Ralli R, et al. The effects of gemfibrozil on serum lipids in diabetic patients. Ann Clin Res 1979; 11:240-245.
Kurtz SM, Fitzgerald JE, Fisken, RA, et al. Toxicological studies on gemfibrozil. Proc Roy Soc Med 1976; 69(Suppl 2):15-23.
Leiss O, von Bergmann K, Gnasso A, et al. Effects of gemfibrozil on biliary lipid metabolism in normolipemic subjects. Metabolism 1985; 34:74-82.
Lewis J and Multicenter Collaborative Study Group. Clinical use of gemfibrozil: A controlled multicenter trial. Practical Cardiology 1983; 9(6):99-118.
Lewis J. Long-term use of gemfibrozil (Lopid) in the treatment of dyslipidemia. Angiology 1982; 33(9):603-612.
Lupien P, Brun D, Gagne C, et al. Gemfibrozil therapy in primary type II hyperlipoproteinemia: Effects on lipids, lipoproteins and apolipoproteins. Can J Cardiol 1991; 7:27-33.
Manninen V, Elo O, Frick M, et al. Lipid alterations and decline in the incidence of coronary heart disease in the Helsinki Heart Study. JAMA 1988; 260:641-651.
Manninen V, Tenkanen L, Koskinen P, et al. Joint effects of serum triglyceride and LDL cholesterol and HDL cholesterol concentrations on coronary heart disease risk in the Helsinki Heart Study. Circulation 1992; 85:37-45.
Manttari M, Koskinen P, Manninen V, et al. Effect of gemfibrozil on the concentration and composition of serum lipoproteins. A controlled study with special reference to initial triglyceride levels. Atherosclerosis 1990; 81:11-17.
Meinertz H. Effects of gemfibrozil on plasma lipoproteins in patients with type II hyperlipoproteinaemia and familial hypercholesterolaemia. R Soc Med Int Congr Symp Ser 1986; 87: 15-21.
Nash D. Gemfibrozil - a new lipid lowering agent. J Med 1980; 11:106-116.
Nash D. Hyperlipoproteinemia, atherosclerosis and gemfibrozil. Angiology 1982; 33(9):594-602.
Niemi M, Backman JT, Neuvonen M, et al. Effects of gemfibrozil, itraconazole, and their combination on the pharmacokinetics and pharmacodynamics of repaglinide: potentially hazardous interaction between gemfibrozil and repaglinide. Diabetologia 2003;46:347-351.
Nikkilia EA. Familial lipoproteins lipase deficiency and related disorders of chylomicron metabolism. In: (Stanbury J et al/eds). The Metabolic Basis of Inherited Disease, 5th ed. McGraw- Hill 1963:pp 622-642.
Nye E, Sutherland W, Temple W. The treatment of hyperlipoproteinemia with gemfibrozil compared with placebo and clofibrate. New Zealand Med J. Nov 12, 1980; 345-349.
Okerholm RA, Keeley FJ, Peterson FE, et al. The metabolism of gemfibrozil. Proc Roy Soc Med 1976; 69(Suppl 2):11-14.
Pasternack A, Vanttinen T, Solakivi T, et al. Normalization of lipoprotein lipase and hepatic lipase by gemfibrozil results in correction of lipoprotein abnormalities in chronic renal failure. Clin Nephrol 1987; 27:163-168.
Rabkin S, Hayden M, Frohlich J. Comparison of gemfibrozil and clofibrate on serum lipids in familial combined hyperlipidemia: A randomized placebo-controlled, double-blind, crossover clinical trial. Atherosclerosis 1988; 73:233-240.
Romm P, Green C, Reagan K, et al. Relation of serum lipoprotein cholesterol levels to presence and severity of angiographic coronary artery disease. Am J Cardiol 1991; 67:479-483.
Saku K, Gartside P, Hynd, B, et al. Mechanism of action of gemfibrozil on lipoprotein metabolism. J Clin Invest 1985; 75:1702-1712.
Sommariva D, Branchi A, Pini C, et al. Changes in serum and lipoprotein lipids, and apolipoprotein B and A-1, in patients with different types of primary hyperlipoproteinemia treated with gemfibrozil. Int J Clin Pharm Res 1988; 8:383-392.
Sorisky A, et al. Change in composition of high density lipoprotein during gemfibrozil therapy. Atherosclerosis 1987; 67:181-189.
Testori G, Ferrari C, Lepore R, et al. Effect of gemfibrozil treatment on glucose tolerance in hypertriglyceridemic patients with normal or impaired glucose tolerance. Curr Ther Res 1990; 47:390-395.
Todd P, Ward A. Gemfibrozil: A review of its pharmacodynamic and pharmacokinetic properties, and therapeutic use in dyslipidemia. Drugs 1988; 36:314-339.
Virtamo J, Manninen V, Malkonen M. A placebo-controlled rising-dose, double-blind trial with gemfibrozil in dieting patients with primary hyperlipoproteinemia. Vascular Medicine 1984; 2:22- 27.
Weintraub M, Eisenberg S, Breslow J. Different patterns of postprandial lipoprotein metabolism in normal, type IIa, type III, and type IV hyperlipoproteinemic individuals: effects of treatment with cholestyramine and gemfibrozil. J Clin Invest 1987; 79:1110-1119.
Product Monograph. Lopid® (Gemfibrozil Capsules USP 300 mg, Gemfibrozil Tablets 600 mg). January 22, 2010.