


Product Monograph - Naproxen - 250
RECENT MAJOR LABEL CHANGES
| 2 CONTRAINDICATIONS | 11/2023 |
|---|---|
| 3 SERIOUS WARNING AND PRECAUTIONS BOX | 11/2023 |
| 7 WARNINGS AND PRECAUTIONS | 11/2023 |
| 7 WARNINGS AND PRECAUTIONS, 7.1.1 Pregnant Women | 11/2023 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................. 2
TABLE OF CONTENTS ............................................................................................................... 2
PART I: HEALTH PROFESSIONAL INFORMATION ....................................................................... 4
1 INDICATIONS ................................................................................................................... 4
1.1 Pediatrics .................................................................................................................... 4
1.2 Geriatrics .................................................................................................................... 4
2 CONTRAINDICATIONS ....................................................................................................... 5
3 SERIOUS WARNINGS AND PRECAUTIONS BOX .................................................................. 6
4 DOSAGE AND ADMINISTRATION ....................................................................................... 7
4.1 Dosing Considerations ................................................................................................ 7
4.2 Recommended Dose and Dosage Adjustment ........................................................... 7
4.4 Administration ............................................................................................................ 8
4.5 Missed Dose ............................................................................................................... 8
5 OVERDOSAGE ................................................................................................................... 9
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING..................................... 10
7 WARNINGS AND PRECAUTIONS ...................................................................................... 10
7.1 Special Populations ................................................................................................... 18
7.1.1 Pregnant Women ..................................................................................................... 18
7.1.2 Breast-feeding .......................................................................................................... 19
7.1.3 Pediatrics .................................................................................................................. 19
7.1.4 Geriatrics .................................................................................................................. 19
8 ADVERSE REACTIONS ...................................................................................................... 20
8.1 Adverse Reaction Overview ...................................................................................... 20
8.2 Clinical Trial Adverse Drug Reactions ........................................................................ 20
8.3 Less Common Clinical Trial Adverse Reactions ......................................................... 21
8.5 Post-Market Adverse Reactions ............................................................................... 22
9 DRUG INTERACTIONS ...................................................................................................... 24
9.3 Drug- Behavioural Interactions ................................................................................. 24
9.4 Drug-Drug Interactions ............................................................................................. 24
9.5 Drug-Food Interactions ............................................................................................. 29
9.6 Drug-Herb Interactions ............................................................................................. 29
9.7 Drug-Laboratory Test Interactions ............................................................................ 30
10 CLINICAL PHARMACOLOGY ............................................................................................. 30
10.1 Mechanism of Action ................................................................................................ 30
10.2 Pharmacodynamics .................................................................................................. 30
10.3 Pharmacokinetics ..................................................................................................... 31
11 STORAGE, STABILITY AND DISPOSAL ............................................................................... 32
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................ 32
PART II: SCIENTIFIC INFORMATION ........................................................................................ 33
13 PHARMACEUTICAL INFORMATION ................................................................................. 33
14 CLINICAL TRIALS .............................................................................................................. 33
14.2 Comparative Bioavailability Studies.......................................................................... 33
15 MICROBIOLOGY .............................................................................................................. 34
16 NON-CLINICAL TOXICOLOGY ........................................................................................... 34
17 SUPPORTING PRODUCT MONOGRAPHS.......................................................................... 37
PATIENT MEDICATION INFORMATION ................................................................................... 38
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
NAPROXEN (naproxen) is indicated for:
- The treatment of the signs and symptoms of osteoarthritis, rheumatoid arthritis, and ankylosing spondylitis.
- The relief of minor aches and pains in muscles, bones and joints, mild to moderate pain accompanied by inflammation in musculoskeletal injuries (sprains and strains) and primary dysmenorrhea.
For patients with an increased risk of developing cardiovascular and/or gastrointestinal adverse events, other management strategies that do NOT include the use of NSAIDs should be considered first. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS.
Use of NAPROXEN should be limited to the lowest effective dose for the shortest possible duration of treatment in order to minimize the potential risk for cardiovascular or gastrointestinal adverse events. See 2 CONTRAINDICATIONS and 7 WARNINGS AND PRECAUTIONS
NAPROXEN, as a NSAID, does NOT treat clinical disease or prevent its progression.
NAPROXEN, as a NSAID, only relieves symptoms and decreases inflammation for as long as the patient continues to take it.
1.1 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of naproxen in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS
1.2 Geriatrics
Geriatrics (> 65 years of age): Evidence from clinical studies and experience suggests that use in the geriatric population is associated with differences in safety or effectiveness. See 4 DOSAGE AND ADMINISTRATION and 7.1.4 Geriatrics.
2 CONTRAINDICATIONS
NAPROXEN is contraindicated in:
- the peri-operative setting of coronary artery bypass graft surgery (CABG). Although naproxen has NOT been studied in this patient population, a selective COX-2 inhibitor NSAID studied in such a setting has led to an increased incidence of cardiovascular/thromboembolic events, deep surgical infections and sternal wound complications.
- the third trimester of pregnancy, because of risk of premature closure of the ductus arteriosus and prolonged parturition
- women who are breastfeeding, because of the potential for serious adverse reactions in nursing infants
- severe uncontrolled heart failure
- patients who are hypersensitive to this drug or to any ingredient in the formulation, including any non-medicinal ingredient, or component of the container. For a complete listing, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
- history of asthma, urticaria, or allergic-type reactions after taking ASA or other NSAIDs (i.e. complete or partial syndrome of ASA-intolerance-rhinosinusitis, urticaria/angioedema, nasal polyps, asthma). Fatal anaphylactoid reactions have occurred in such individuals. Individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse reaction. The potential for cross-reactivity between different NSAIDs must be kept in mind. See 7 WARNINGS AND PRECAUTIONS, Sensitivity/Resistance, Anaphylactoid Reactions
- active gastric / duodenal / peptic ulcer, active GI bleeding.
- cerebrovascular bleeding or other bleeding disorders
- inflammatory bowel disease
- severe liver impairment or active liver disease
- severe renal impairment (creatinine clearance <30 mL/min or 0.5 mL/sec) or deteriorating renal disease (individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored). See 7 WARNINGS AND PRECAUTIONS, Renal
- known hyperkalemia. See 7 WARNINGS AND PRECAUTIONS, Renal, Fluid and Electrolyte Balance
- children and adolescents less than 18 years of age since naproxen has not been studied in subjects under the age of 18.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
|
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
- Use of NAPROXEN should be limited to the lowest effective dose for the shortest possible duration of treatment. See 1 INDICATIONS.
- For all indications, treatment must be initiated with the lowest dose. Other 250 mg naproxen formulations are available for the 250 mg tablet starting dose.
- Caution should be exercised in prescribing NAPROXEN to any patient with ischemic heart disease (including but NOT limited to acute myocardial infarction, history of myocardial infarction and/or angina), cerebrovascular disease (including but NOT limited to stroke, cerebrovascular accident, transient ischemic attacks and/or amaurosis fugax) and/or congestive heart failure (NYHA II-IV). See 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
- A lower dose should be considered in patients with renal or hepatic impairment or in elderly patients.
4.2 Recommended Dose and Dosage Adjustment
Adult:
Osteoarthritis / Rheumatoid Arthritis / Ankylosing Spondylitis
The usual total dosage of naproxen for osteoarthritis, rheumatoid arthritis, and ankylosing spondylitis is 250 mg twice a day. It may be increased gradually to 375 mg or 500 mg twice a day, depending on the patient’s response.
| Recommended Daily Dosing | ||
|---|---|---|
| NAPROXEN (Tablets) | 250 mg or 375 mg or 500 mg | twice daily twice daily twice daily |
Studies have not shown any clinically significant benefit in using doses higher than 1000 mg/day. In patients who tolerate lower doses of naproxen well and who exhibit only a partial response to 1000 mg/day, the dose may be increased to 1500 mg/day for limited periods. Experience with 1500 mg/day naproxen is limited to using the standard tablets.
When treating such patients with naproxen 1500 mg/day, the physician should observe sufficient increased clinical benefit to offset the potential increased risk. See 8 ADVERSE REACTIONS
In addition, patients on 1500 mg/day need to be followed closely for the development of any adverse events.
During long–term administration, the dose of NAPROXEN may be adjusted up or down depending on the clinical response of the patient. A lower dose may suffice for long–term administration.
Analgesia / Musculoskeletal Injuries
The recommended dose for naproxen is 250 mg three times a day or 375 mg twice a day. This may be increased to 500 mg twice a day if needed. The lowest effective dose should be used.
Dysmenorrhea
The recommended starting dose for naproxen is two 250 mg tablets (or one 500 mg tablet), followed by one 250 mg tablet every 6 to 8 hours, as required. The total daily dose should not exceed 5 tablets (1250 mg). Alternatively, one 500 mg tablet given twice daily may be used.
Pediatrics (< 18 years of age): Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS
Geriatrics (>65 years of age): In the elderly, frail and debilitated, the dosage should be reduced to the lowest level providing control of symptoms, and adjusted when necessary. See 7.1.4 Geriatrics
Renal impairment: A lower dose should be considered in patients with mild and moderate renal impairment. NAPROXEN is contraindicated in severe renal impairment (creatinine clearance <30 mL/min or 0.5 mL/sec) or deteriorating renal disease (individuals with lesser degrees of renal impairment are at risk of deterioration of their renal function when prescribed NSAIDs and must be monitored). See 2 CONTRAINDICATIONS
Hepatic impairment: A lower dose should be considered in patients with mild and moderate hepatic impairment. NAPROXEN is contraindicated in severe liver impairment or active liver disease. See 2 CONTRAINDICATIONS
4.4 Administration
NAPROXEN tablets should be swallowed whole.
4.5 Missed Dose
If a dose is missed, the patient should take it as soon as it is recognized. If it is almost time for the next dose, skip the missed dose and continue with the next scheduled dose. The patient should be instructed not take 2 doses at the same time.
5 OVERDOSAGE
Frequently observed signs and symptoms of overdose are drowsiness, dizziness, disorientation, heartburn, indigestion, epigastric pain, abdominal discomfort, nausea, vomiting, transient alterations in liver function, hypoprothrombinemia, renal dysfunction, metabolic acidosis and apnea. A few patients have experienced convulsions, but it is not clear whether or not these were naproxen related.
Gastrointestinal bleeding may occur. Hypertension, acute renal failure, respiratory depression and coma may occur after the ingestion of NSAIDs but are rare.
Anaphylactoid reactions have been repeated with therapeutic ingestion of NSAIDs, and may occur following an overdose.
Patients should be managed by symptomatic and supportive care following NSAIDs overdose. There are no specific antidotes. Prevention of further absorption (e.g. activated charcoal) may be indicated in patients seen within 4 hours of ingestion with symptoms or following a large overdose. Forced diuresis, alkalinization of urine, haemodialysis, or haemoperfusion may not be useful due to high protein binding.
| For management of a suspected drug overdose, contact your regional poison control centre. |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form / Strength / Composition | Non-medicinal Ingredients |
|---|---|---|
| Oral | Tablets, 250 mg, 375 mg and 500 mg | Colloidal silicon dioxide, croscarmellose sodium, magnesium stearate and methylcellulose. The 250 and the 500 mg tablets also contain D&C yellow #10 and FD&C yellow #6; the 375 mg tablets contain only FD&C yellow #6; |
Description
NAPROXEN is available as:
Tablets: NAPROXEN 250 mg tablets: Each yellow, oval, biconvex tablet engraved “APO-250” on one side contains 250 mg naproxen. Available in bottles of 100 tablets.
NAPROXEN 375 mg tablets: Each peach-coloured, capsule-shaped, biconvex tablet, scored and engraved “APO 375” on one side, contains 375 mg naproxen. Available in bottles of 100 tablets.
NAPROXEN 500 mg tablets: Each yellow, capsule-shaped, biconvex tablet, scored and engraved “APO 500” on one side, contains 500 mg naproxen. Available in bottles 500 tablets.
7 WARNINGS AND PRECAUTIONS
Please see 3 SERIOUS WARNINGS AND PRECAUTIONS BOX
General
Frail or debilitated patients may tolerate side effects less well and therefore special care should be taken in treating this population. To minimize the potential risk for an adverse event, the lowest effective dose should be used for the shortest possible duration. As with other NSAIDs, caution should be used in the treatment of elderly patients who are more likely to be suffering from impaired renal, hepatic or cardiac function. For high-risk patients, alternate therapies that do not involve NSAIDs should be considered.
NAPROXEN is NOT recommended for use with other NSAIDs, with the exception of low-dose ASA for cardiovascular prophylaxis, because of the absence of any evidence demonstrating synergistic benefits and the potential for additive adverse reactions. See 9.4 Drug-Drug Interactions, Acetylsalicylic acid (ASA) or other NSAIDs
NAPROXEN (naproxen) should not be used concomitantly with the related drug naproxen sodium since they both circulate in plasma as the naproxen anion.
Carcinogenesis and Mutagenesis
See 16 NON-CLINICAL TOXICOLOGY
Cardiovascular
NAPROXEN is a non-steroidal anti-inflammatory drug (NSAID). Use of some NSAIDs is associated with an increased incidence of cardiovascular adverse events (such as myocardial infarction, stroke or thrombotic events) which can be fatal. The risk may increase with duration of use. Patients with cardiovascular disease or risk factors for cardiovascular disease may be at greater risk.
Caution should be exercised in prescribing NAPROXEN to patients with risk factors for cardiovascular disease, cerebrovascular disease or renal disease, such as any of the following (NOT an exhaustive list)
- Hypertension
- Dyslipidemia / Hyperlipidemia
- Diabetes Mellitus
- Congestive Heart Failure (NYHA I)
- Coronary Artery Disease (Atherosclerosis)
- Peripheral Arterial Disease
- Smoking
- Creatinine Clearance < 60 mL/min or 1 mL/sec
Use of NSAIDs, such as NAPROXEN, can lead to new hypertension or can worsen pre-existing hypertension, either of which may increase the risk of cardiovascular events as described above. Thus, blood pressure should be monitored regularly. Consideration should be given to discontinuing NAPROXEN should hypertension either develop or worsen with its use.
Use of NSAIDs, such as NAPROXEN, can induce fluid retention and edema, and may exacerbate congestive heart failure, through a renally-mediated mechanism.
For patients with a high risk of developing an adverse CV event, other management strategies that do NOT include the use of NSAIDs should be considered first. To minimize the potential risk for an adverse CV event, the lowest effective dose should be used for the shortest possible duration.
Driving and Operating Machinery
There are no specific studies about effects on the ability to drive vehicles and to use machinery. Patients who experience visual disturbances or other central nervous system disturbances should refrain from these activities.
Endocrine and Metabolism
Corticosteroids: NAPROXEN is NOT a substitute for corticosteroids. It does NOT treat corticosteroid insufficiency. Abrupt discontinuation of corticosteroids may lead to exacerbation of corticosteroid-responsive illness. Patients on prolonged corticosteroid therapy should have their therapy tapered slowly if a decision is made to discontinue corticosteroids. See 9.4 Drug-Drug Interactions, Glucocorticoids
Gastrointestinal
Serious GI toxicity (sometimes fatal), such as ulceration, inflammation, gastrointestinal bleeding, perforation and obstruction of the upper and lower gastrointestinal tract, can occur at any time, with or without warning symptoms, in patients treated with NSAIDs, such as NAPROXEN. Minor upper GI problems, such as dyspepsia, commonly occur at any time. Health care providers should remain alert for ulceration and bleeding in patients treated with NAPROXEN, even in the absence of previous GI tract symptoms. Most spontaneous reports of fatal GI events are in elderly or debilitated patients and therefore special care should be taken in treating this population. To minimize the potential risk for an adverse GI event, the lowest effective dose should be used for the shortest possible duration. For high-risk patients, alternate therapies that do not involve NSAIDs should be considered. See 7.1.4 Geriatrics
Patients should be informed about the signs and/or symptoms of serious GI toxicity and instructed to discontinue using NAPROXEN and seek emergency medical attention if they experience any such symptoms. The utility of periodic laboratory monitoring has NOT been demonstrated, nor has it been adequately assessed. Most patients who develop a serious upper GI adverse event on NSAID therapy have no symptoms. Upper GI ulcers, gross bleeding or perforation, caused by NSAIDs, appear to occur in approximately 1% of patients treated for 3 to 6 months, and in about 2 to 4% of patients treated for one year. These trends continue, thus increasing the likelihood of developing a serious GI event at some time during the course of therapy. Even short-term therapy has its risks.
Caution should be taken if prescribing NAPROXEN to patients with a prior history of peptic / duodenal ulcer disease or gastrointestinal bleeding as these individuals have a greater than 10- fold higher risk for developing a GI bleed when taking a NSAID than patients with neither of these risk factors. Other risk factors for GI ulceration and bleeding include the following: Helicobacter pylori infection, increased age, prolonged use of NSAID therapy, excess alcohol intake, smoking, poor general health status or concomitant therapy with any of the following:
- Anti-coagulants (e.g., warfarin)
- Anti-platelet agents (e.g., ASA, clopidogrel)
- Oral corticosteroids (e.g., prednisone)
- Selective Serotonin Reuptake Inhibitors (SSRIs) (e.g., citalopram, fluoxetine, paroxetine, sertraline)
Genitourinary
Some NSAIDs are associated with persistent urinary symptoms (bladder pain, dysuria, urinary frequency), hematuria or cystitis. The onset of these symptoms may occur at any time after the initiation of therapy with a NSAID. Should urinary symptoms occur, in the absence of an alternate explanation, treatment with NAPROXEN should be stopped to ascertain if symptoms disappear. This should be done before urological investigations or treatments are carried out.
Hematologic
NSAIDs inhibiting prostaglandin biosynthesis interfere with platelet function to varying degrees; patients who may be adversely affected by such an action, such as those on anti-coagulants or suffering from haemophilia or platelet disorders should be carefully observed when NAPROXEN is administered.
Anti-coagulants: Numerous studies have shown that the concomitant use of NSAIDs and anticoagulants increases the risk of bleeding. Concurrent therapy of NAPROXEN with warfarin requires close monitoring of the international normalized ratio (INR).
Even with therapeutic INR monitoring, increased bleeding may occur. See 9 DRUG INTERACTIONS
Anti-platelet Effects: NSAIDs inhibit platelet aggregation and have been shown to prolong bleeding time in some patients. Unlike acetylsalicylic acid (ASA), their effect on platelet function is quantitatively less, or of shorter duration, and is reversible.
NAPROXEN and other NSAIDs have no proven efficacy as anti-platelet agents and should NOT be used as a substitute for ASA or other anti-platelet agents for prophylaxis of cardiovascular thromboembolic diseases. Anti-platelet therapies (e.g., ASA) should NOT be discontinued. There is some evidence that use of NSAIDs with ASA can markedly attenuate the cardioprotective effects of ASA. See 9.4 Drug-Drug Interactions, Acetylsalicylic Acid or other
NSAIDs
Concomitant administration of NAPROXEN with low dose ASA increases the risk of GI ulceration and associated complications.
Blood dyscrasias: Blood dyscrasias (such as neutropenia, leukopenia, thrombocytopenia, aplastic anemia and agranulocytosis) associated with the use of NSAIDs are rare, but could occur with severe consequences.
Anemia is sometimes seen in patients receiving NSAIDs, including naproxen. This may be due to fluid retention, GI blood loss, or an incompletely described effect upon erythropoiesis. Patients on long-term treatment with NSAIDs, including NAPROXEN, should have their hemoglobin or hematocrit checked if they exhibit any signs or symptoms of anemia or blood loss.
Hepatic/Biliary/Pancreatic
As with other NSAIDs, borderline elevations of one or more liver enzyme tests (AST, ALT, alkaline phosphatase) may occur in up to 15% of patients. These abnormalities may progress, may remain essentially unchanged, or may be transient with continued therapy.
Chronic alcoholic liver disease and probably also other forms of cirrhosis reduce the total plasma concentration of naproxen, but the plasma concentration of unbound naproxen is increased. The implication of this finding for naproxen dosing is unknown, but caution is advised when high doses are required. It is prudent to use the lowest effective dose.
A patient with symptoms and/or signs suggesting liver dysfunction, or in whom an abnormal liver function test has occurred, should be evaluated for evidence of the development of a more severe hepatic reaction while on therapy with this drug. Severe hepatic reactions including jaundice and cases of fatal hepatitis, liver necrosis and hepatic failure, some of them with fatal outcomes, have been reported with NSAIDs.
Although such reactions are rare, if abnormal liver tests persist or worsen, if clinical signs and symptoms consistent with liver disease develop (e.g., jaundice), or if systemic manifestations occur (e.g., eosinophilia, associated with rash, etc.), this drug should be discontinued.
If there is a need to prescribe this drug in the presence of impaired liver function, it must be done under strict observation.
Immune
NAPROXEN, in common with other NSAIDs, may mask signs and symptoms of an underlying infectious disease.
Aseptic Meningitis: Rarely, with some NSAIDs, the symptoms of aseptic meningitis (stiff neck, severe headaches, nausea and vomiting, fever or clouding of consciousness) have been observed. Patients with autoimmune disorders (systemic lupus erythematosus, mixed connective tissue diseases, etc.) seem to be pre-disposed. Therefore, in such patients, the health care provider must be vigilant to the development of this complication.
Monitoring and Laboratory Tests
Cardiovascular: Patients on long-term treatment with NAPROXEN should have their blood pressure monitored regularly and an ophthalmic examination should be carried out at periodic intervals.
Hematology: Hemoglobin, hematocrit, red blood cells (RBCs), white blood cells (WBCs), and platelets should be checked in patients on long-term treatment with NAPROXEN. Additionally, concurrent therapy with warfarin requires close monitoring of the international normalized ratio (INR).
Hepatic: Serum transaminase and bilirubin should be monitored regularly during NAPROXEN therapy.
Renal: Serum creatinine, creatine clearance and serum urea should be checked in patient during NAPROXEN therapy. Electrolytes including serum potassium should be monitored periodically.
Pregnancy: If NAPROXEN is administered in the middle (approximately 20 weeks) to the end of the second trimester, it is recommended that pregnant women on NAPROXEN be closely monitored for amniotic fluid volume since NAPROXEN may result in reduction of amniotic fluid volume and even oligohydramnios. See 7.1.1 Pregnant Women
NAPROXEN is contraindicated for use in the third trimester of pregnancy.
Neurologic
Some patients may experience drowsiness, dizziness, blurred vision, vertigo, tinnitus, hearing loss, insomnia or depression with the use of NSAIDs, such as NAPROXEN. If patients experience such adverse reaction(s), they should exercise caution in carrying out activities that require alertness.
Ophthalmologic
Blurred and/or diminished vision has been reported with the use of NSAIDs. If such symptoms develop, NAPROXEN should be discontinued and an ophthalmologic examination performed.
Ophthalmologic examination should be carried out at periodic intervals in any patient receiving NAPROXEN for an extended period of time.
Peri-Operative Considerations
See 2 CONTRAINDICATIONS
Psychiatric
Some patients may experience depression with the use of NSAIDs, such as naproxen.
Renal
Long term administration of NSAIDs to animals has resulted in renal papillary necrosis and other abnormal renal pathology. In humans, there have been reports of acute interstitial nephritis, hematuria, low grade proteinuria and occasionally nephrotic syndrome.
Renal insufficiency due to NSAID use is seen in patients with pre-renal conditions leading to reduction in renal blood flow or blood volume. Under these circumstances, renal prostaglandins help maintain renal perfusion and glomerular filtration rate (GFR). In these patients, administration of a NSAID may cause a reduction in prostaglandin synthesis leading to impaired renal function. Patients at greatest risk of this reaction are those with pre-existing renal insufficiency (GFR < 60 mL/min or 1 mL/s), dehydrated patients, patients on salt restricted diets, those with congestive heart failure, cirrhosis, liver dysfunction, taking angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, cyclosporin, diuretics, and those who are elderly. Serious or life-threatening renal failure has been reported in patients with normal or impaired renal function after short term therapy with NSAIDs.
Even patients at risk who demonstrate the ability to tolerate a NSAID under stable conditions may decompensate during periods of added stress (e.g., dehydration due to gastroenteritis). Discontinuation of NSAIDs is usually followed by recovery to the pre-treatment state.
Caution should be used when initiating treatment with NSAIDs, such as NAPROXEN, in patients with considerable dehydration. Such patients should be rehydrated prior to initiation of therapy. Caution is also recommended in patients with pre-existing kidney disease.
Advanced Renal Disease: See 2 CONTRAINDICATIONS
Fluid and Electrolyte Balance: Use of NSAIDs, such as NAPROXEN, can promote sodium retention in a dose-dependent manner, which can lead to fluid retention and edema, and consequences of increased blood pressure and exacerbation of congestive heart failure. Thus, caution should be exercised in prescribing NAPROXEN in patients with a history of congestive heart failure, compromised cardiac function, hypertension, increased age or other conditions predisposing to fluid retention.
Use of NSAIDs, such as NAPROXEN, can increase the risk of hyperkalemia, especially in patients with diabetes mellitus, renal failure, increased age, or those receiving concomitant therapy with adrenergic blockers, angiotensin-converting enzyme inhibitors, angiotensin-II receptor antagonists, cyclosporin, or some diuretics.
Electrolytes should be monitored periodically. See 2 CONTRAINDICATIONS
Reproductive Health: Female and Male Potential
Fertility
The use of NAPROXEN, as with any drug known to inhibit cyclooxygenase/prostaglandin synthesis, may impair fertility and is not recommended in women attempting to conceive. Therefore, in women who have difficulties conceiving, or who are undergoing investigation of infertility, withdrawal of NAPROXEN should be considered. See 7.1.1 Pregnant Women
Respiratory
ASA-induced asthma is an uncommon but very important indication of ASA and NSAID sensitivity. It occurs more frequently in patients with asthma who have nasal polyps.
Sensitivity/Resistance
Anaphylactoid Reactions: As with NSAIDs in general, anaphylactoid reactions have occurred in patients without known prior exposure to naproxen. In post-marketing experience, rare cases of anaphylactic/ anaphylactoid reactions and angioedema have been reported in patients receiving naproxen. NAPROXEN should NOT be given to patients with the ASA-triad. This symptom complex typically occurs in asthmatic patients who experience rhinitis with or without nasal polyps, or who exhibit severe, potentially fatal bronchospasm after taking ASA or other NSAIDs. See 2 CONTRAINDICATIONS
ASA-Intolerance: NAPROXEN should NOT be given to patients with complete or partial syndrome of ASA-intolerance (rhinosinusitis, urticaria/angioedema, nasal polyps, asthma) in whom asthma, anaphylaxis, urticaria/angioedema, rhinitis or other allergic manifestations are precipitated by ASA or other NSAIDs. Fatal anaphylactoid reactions have occurred in such individuals. As well, individuals with the above medical problems are at risk of a severe reaction even if they have taken NSAIDs in the past without any adverse reaction. See 2 CONTRAINDICATIONS
Cross-sensitivity: Patients sensitive to one NSAID may be sensitive to any of the other NSAIDs as well.
Skin
Serious skin reactions: Use of some NSAIDs, such as naproxen, have been associated with rare post-market cases of serious, fatal or otherwise life-threatening skin reactions, including:
- Drug reaction with eosinophilia and systemic symptoms (DRESS)
- Stevens-Johnson syndrome (SJS)
- toxic epidermal necrolysis (TEN)
- exfoliative dermatitis
- erythema multiforme.
Patients appear to be at higher risk for these events early in the course of therapy, with the onset of cases usually occurring within the first month of treatment. These reactions may be reversible if the causative agent is discontinued and appropriate treatment instituted. Patients should be advised that they should discontinue their NSAID at the first appearance of a skin rash, mucosal lesions or any other sign of hypersensitivity, and contact their physician immediately for assessment and advice, including which therapies to discontinue.
DRESS typically, although not exclusively, presents with fever, rash, lymphadenopathy, and/or facial swelling. Other clinical manifestations may include hepatitis, nephritis, hematological abnormalities, myocarditis, or myositis. Sometimes symptoms of DRESS may resemble an acute viral infection, and eosinophilia is often present. Because this disorder is variable in its presentation, other organ systems not noted here may be involved. It is important to note that early manifestations of hypersensitivity, such as fever or lymphadenopathy, may be present even though rash is not evident.
7.1 Special Populations
7.1.1 Pregnant Women
NAPROXEN is contraindicated for use during the third trimester of pregnancy because of risks of premature closure of the ductus arteriosus and the potential to prolong parturition. See 2 CONTRAINDICATIONS and 16 NON-CLINICALTOXICOLOGY. Caution is recommended in prescribing NAPROXEN during the first and second trimesters of pregnancy, particularly from the middle to end of the second trimester of pregnancy (onset at approximately 20 weeks) due to possible fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment or failure.
Published studies and postmarketing reports describe maternal NSAID use at approximately 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment or failure. NSAIDs were shown to cause significant reduction in fetal urine production prior to reduction of amniotic fluid volume. There have also been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction and renal impairment without oligohydramnios, some of which were irreversible, even after treatment discontinuation.
These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation.
Complications of prolonged oligohydramnios may for example, include limb contractures and delayed lung maturation. In some postmarketing cases of impaired neonatal renal function, invasive procedures such as exchange transfusion or dialysis were required.
If after careful consideration of the benefit-risk, NSAID treatment is considered necessary to be administered anywhere from the middle (onset at approximately 20 weeks) to the end of the second trimester of pregnancy, the use should be limited to the lowest effective dose and shortest duration possible. It is also recommended that ultrasound monitoring of amniotic fluid be considered if NAPROXEN treatment extends beyond 48 hours and that NSAIDs treatment be discontinued if oligohydramnios occurs, followed by appropriate medical follow up.
Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or embryo-foetal development. Data from epidemiological studies suggest an increased risk of miscarriage and of cardiac malformation after use of a prostaglandin synthesis inhibitor in early pregnancy.
In animals, administration of a prostaglandin synthesis inhibitor has been shown to result in increased pre- and post-implantation loss and embryo-foetal lethality. In addition, increased incidences of various malformations, including cardiovascular, have been reported in animals given a prostaglandin synthesis inhibitor during the organogenetic period.
NAPROXEN is not recommended in labour and delivery because, through their prostaglandin synthesis inhibitory effect, they may adversely affect fetal circulation and inhibit uterine contractions, thus increasing the risk of uterine hemorrhage.
7.1.2 Breast-feeding
NAPROXEN is contraindicated in breast-feeding women. See 2 CONTRAINDICATIONS
7.1.3 Pediatrics
Pediatrics (< 18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of naproxen in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS
7.1.4 Geriatrics
Geriatrics (> 65 years of age): Patients older than 65 years (referred to in this document as older or elderly) and frail or debilitated patients are more susceptible to a variety of adverse reactions from NSAIDs. The incidence of these adverse reactions increases with dose and duration of treatment. In addition, these patients are less tolerant to ulceration and bleeding. Most reports of fatal GI events are in this population. Older patients are also at risk of lower esophageal injury including ulceration and bleeding. For such patients, consideration should be given to a starting dose lower than the one usually recommended, with individual adjustment when necessary and under close supervision. See 7 WARNINGS AND PRECAUTIONS
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The most common adverse reactions encountered with non-steroidal anti-inflammatory drugs are gastrointestinal, of which peptic ulcer, with or without bleeding, is the most severe. Fatalities have occurred particularly in the elderly.
As with all drugs in this class, the frequency and severity of adverse events depends on several factors: the dose of the drug and duration of treatment; the age, the sex, physical condition of the patient; any concurrent medical diagnoses or individual risk factors.
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
A clinical study found gastrointestinal reactions to be more frequent and more severe in rheumatoid arthritis patients taking daily doses of 1500 mg naproxen compared to those taking 750 mg naproxen.
The adverse reactions in controlled clinical trials in 960 patients with rheumatoid arthritis or osteoarthritis treated with the naproxen standard tablets are listed below.
Table 2: Most Common Clinical Trial Adverse Drug Reactions (3% to 9% and 1% to 3%)
| Body System | Incidence | Adverse Reaction |
|---|---|---|
| Gastrointestinal | 3%-9% | Heartburn, constipation, abdominal pain, nausea |
| 1%-3% | Diarrhea, dyspepsia, stomatitis, diverticulitis, gastrointestinal bleeding | |
| Central Nervous System | 3%-9% | Headache, dizziness, drowsiness |
| Body System | Incidence | Adverse Reaction |
|---|---|---|
| 1%-3% | Light-headedness, vertigo, depression, fatigue. Occasionally patients had to discontinue treatment because of the severity of some of these complaints (headache and dizziness). | |
| Dermatologic | 3%-9% | Pruritus, ecchymoses, skin eruptions |
| 1%-3% | Sweating, purpura | |
| Cardiovascular | 3%-9% | Dyspnea, peripheral edema |
| 1%-3% | Palpitations | |
| Special Senses | 3%-9% | Tinnitus |
| 1%-3% | Hearing disturbances | |
| General | 1%-3% | Thirst |
8.3 Less Common Clinical Trial Adverse Reactions
Table 3: Less Common Clinical Trial Adverse Drug Reactions (<1%)
| Gastrointestinal | gastrointestinal bleeding, hematemesis, melena, peptic ulceration with or without bleeding and/or perforation, vomiting, ulcerative stomatitis. |
|---|---|
| Central Nervous System | inability to concentrate, malaise, myalgia, insomnia and cognitive dysfunction (i.e. decreased attention span, loss of short-term memory, difficulty with calculations). |
| Dermatologic | alopecia, urticaria, skin rash, erythema multiforme, Stevens-Johnson syndrome, epidermal necrolysis, photosensitive dermatitis, exfoliative dermatitis, erythema nodosum. |
| Hepatic | abnormal liver function tests, jaundice, cholestasis and hepatitis. |
| Cardiovascular | congestive heart failure and vasculitis. |
| Renal | glomerular nephritis, hematuria, interstitial nephritis, nephrotic syndrome, nephropathy and tubular necrosis. |
| Hematologic | eosinophilia, granulocytopenia, leukopenia, thrombocytopenia, agranulocytosis, aplastic anemia and hemolytic anemia. |
| Special Senses | hearing impairment and visual disturbances. |
| Reproductive, female | infertility |
| General | muscle weakness, anaphylactoid reactions, menstrual disorders, pyrexia (chills and fever), angioneurotic edema, hyperglycemia, hypoglycemia and eosinophilic pneumonitis. |
|---|
8.5 Post-Market Adverse Reactions
Additional reports of serious adverse events temporally associated with naproxen during worldwide post-marketing experience are included below. Because these events are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or clearly establish a causal relationship to naproxen exposure.
| Gastrointestinal: | Inflammation, bleeding (sometimes fatal, particularly in the elderly), ulceration, perforation and obstruction of the upper or lower gastrointestinal tract. Oesophagitis, gastritis, pancreatitis, stomatitis. Exacerbation of ulcerative colitis and Crohn’s disease. Heartburn, dyspepsia, abdominal pain, nausea, vomiting, diarrhoea, flatulence, constipation, haematemesis, melaena. |
|---|---|
| Infections: | aseptic meningitis |
| Blood and Lymphatic System Disorders: | agranulocytosis, aplastic anaemia, eosinophilia, haemolytic anaemia, leucopoenia, thrombocytopenia |
| Immune System Disorders: | anaphylactoid reactions |
| Metabolic and Nutrition Disorders: | hyperkalemia |
| Psychiatric Disorders: | depression, dream abnormalities, insomnia |
| Nervous System Disorders: | dizziness, drowsiness, headache, lightheadedness, retrobulbar optic neuritis convulsions, cognitive dysfunction, inability to concentrate |
| Eye Disorders: | visual disturbances, corneal opacity, papillitis, papilloedema |
| Ear and Labyrinth Disorders: | hearing impairment, hearing disturbances, tinnitus, vertigo |
| Cardiac Disorders: | palpitations, cardiac failure has been reported in association with NSAID treatment, congestive heart failure |
|---|---|
| Vascular Disorders: | hypertension, vasculitis Clinical trial and epidemiological data suggest that use of coxibs and some NSAIDs (particularly at high doses and in long term treatment) may be associated with a small increased risk of arterial thrombotic events (for example myocardial infarction or stroke). |
| Respiratory, Thoracic and Mediastinal Disorders: | dyspnoea, pulmonary oedema, asthma, eosinophilic pneumonitis. |
| Hepatobiliary Disorders: | hepatitis (some cases of hepatitis have been fatal), jaundice. |
| Skin and Subcutaneous Tissue Disorders: | ecchymoses, itching (pruritus), purpura, skin eruptions, sweating, alopecia, epidermal necrolysis, very rarely toxic epidermal necrolysis, erythema multiforme, bullous reactions, including Stevens-Johnson syndrome, erythema nodosum, fixed drug eruption, lichen planus, pustular reaction, skin rashes, SLE, urticaria, photosensitivity reactions, including rare cases resembling porphyria cutanea tarda (“pseudoporphyria”) or epidermolysis bullosa and angioneurotic oedema. If skin fragility, blistering or other symptoms suggestive of pseudoporphyria occur, treatment should be discontinued and the patient monitored. |
| Musculoskeletal and Connective Tissue Disorders: | myalgia, muscle weakness. |
| Renal and Urinary Disorders: | haematuria, interstitial nephritis, nephrotic syndrome, renal disease, renal failure, renal papillary necrosis |
| Reproductive System and Breast Disorders: | female infertility |
| General Disorders and Administration Site Conditions: | oedema, thirst, pyrexia (chills and fever), malaise |
|---|---|
| Investigations: | abnormal liver function tests, raised serum creatinine |
9 DRUG INTERACTIONS
9.3 Drug-Behavioural Interactions
There are no specific studies about effects on the ability to drive vehicles and to use machinery.
Patients who experience visual disturbances or other central nervous system disturbances should refrain from these activities.
Concurrent use of alcohol with an NSAID may increase the risk of gastrointestinal side effects, including ulceration and hemorrhage.
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 4: Established or Potential Drug-Drug Interactions
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Acetylsalicylic acid (ASA) or other NSAIDs | CT |
|
|
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| ACE Inhibitors, Angiotensin Receptor Blockers, and Beta-Blockers | T |
|
|
| Albumin-Bound Drugs | T |
|
|
| Antacids | N/A |
|
|
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Anti-coagulants | CT |
|
|
| Anti-platelets Agents (including ASA) | CT |
|
|
| Cyclosporin and Tacrolimus | T |
|
|
| Cholestyramine | N/A |
|
|
| Digoxin | C |
|
|
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
|---|---|---|---|
| Diuretics | CT |
|
|
| Glucocorticoids | CT |
|
|
| Lithium | CT |
|
|
| Methotrexate | N/A |
|
|
| Pemetrexed | CT |
|
|
| Proper/Common name | Source of Evidence | Effect | Clinical comment | ||||
|---|---|---|---|---|---|---|---|
|
| ||||||
| Probenecid | CT |
|
| ||||
| Selective serotonin reuptake inhibitors (SSRIs) | C |
|
| ||||
| Quinolone antibacterials | C |
|
| ||||
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical; GI = Gastrointestinal; CV = Cardiovascular; INR = International normalized ratio; PD = Pharmacodynamic; ASA = Acetylsalicylic acid; NSAID = Non-Steroidal Anti-Inflammatory Drug; ACE = Angiotensin converting enzyme; ARB = Angiotensin Receptor Blockers; RI = Renal impairment;
9.5 Drug-Food Interactions
Concomitant administration of food can delay the absorption of naproxen but does not affect its extent of absorption.
9.6 Drug-Herb Interactions
Interactions with herbal products have not been established.
9.7 Drug-Laboratory Test Interactions
Bleeding times: Naproxen may decrease platelet aggregation and prolong bleeding time. This effect should be kept in mind when bleeding times are determined.
Porter-Silber test: The administration of naproxen may result in increased urinary values for 17- ketogenic steroids because of an interaction between the drug and/or its metabolites with m- dinitrobenzene used in this assay. Although 17-hydroxy-corticosteroid measurements (Porter- Silber test) do not appear to be artifactually altered, it is suggested that therapy with naproxen be temporarily discontinued 72 hours before adrenal function tests are performed if the Porter- Silber test is to be used.
Urinary assays of 5-hydroxy indoleacetic acid (5HIAA): Naproxen may interfere with some urinary assays of 5-hydroxy indoleacetic acid (5HIAA). This effect should be kept in mind when urinary 5-hydroxy indoleacetic acid is determined.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
NAPROXEN contains naproxen, a propionic acid derivative related to the arylacetic acid group of NSAIDs.
Naproxen is a non-steroidal anti-inflammatory drug (NSAID) with analgesic, anti-inflammatory and antipyretic properties. The mechanism of action of naproxen, like that of other NSAIDs, is not completely understood but may be related to prostaglandin synthetase inhibition.
10.2 Pharmacodynamics
In a healthy volunteer study, 10 days of concomitant administration of naproxen 220 mg once daily with low-dose immediate release aspirin (81 mg) showed an interaction with the antiplatelet activity of aspirin as measured by % serum thromboxane B2 inhibition at 24 hours following the day 10 dose [98.7% (aspirin alone) vs 93.1% (naproxen and aspirin)]. The interaction was observed even following discontinuation of naproxen on day 11 (while aspirin dose was continued) but normalized by day 13. In the same study, the interaction was greater when naproxen was administered 30 minutes prior to aspirin [98.7% vs 87.7%] and minimal when aspirin was administered 30 minutes prior to naproxen [98.7% vs 95.4%].
Following administration of naproxen 220 mg twice-daily with low-dose immediate-release aspirin (first naproxen dose given 30 minutes prior to aspirin), the interaction was minimal at 24 h following day 10 dose [98.7% vs 95.7%]. However, the interaction was more prominent after discontinuation of naproxen (washout) on day 11 [98.7% vs 84.3%] and did not normalize completely by day 13 [98.5% vs 90.7%]. See 9 DRUG INTERACTIONS
10.3 Pharmacokinetics
Absorption
Naproxen is rapidly and completely absorbed from the gastro-intestinal tract. After oral administration of naproxen (standard release), peak plasma levels of naproxen anion are attained in 2 to 4 hours, with steady-state conditions normally achieved after 4 to 5 doses. Plasma naproxen levels and areas under plasma concentration vs. time curves increased linearly with dose increments up to 500 mg twice a day, but larger doses resulted in a plateau effect.
Distribution
Naproxen has a volume of distribution of 0.16 L/kg. At therapeutic levels naproxen is greater than 99% albumin-bound. At doses of naproxen greater than 500 mg/day there is less than proportional increase in plasma levels due to an increase in clearance caused by saturation of plasma protein binding at higher doses.
The naproxen anion has been found in the milk of lactating women at a concentration equivalent to approximately 1% of maximum naproxen concentration in plasma. See 7.1.2 Breast-feeding
Metabolism
Naproxen is extensively metabolized in the liver to 6-0-desmethyl naproxen, and both parent and metabolites do not induce metabolizing enzymes. Both naproxen and 6-0-desmethyl naproxen are further metabolized to their respective acylglucuronide conjugated metabolites.
Elimination
The mean biological half-life of the anion in humans is approximately 13 hours.
The clearance of naproxen is 0.13 mL/min/kg. Approximately 95% of the dose is excreted in the urine, primarily as naproxen, 6-0-desmethyl naproxen or their conjugates. The rate of excretion has been found to coincide closely with the rate of drug disappearance from the plasma. Small amounts, 3% or less of the administered dose, are excreted in the feces. In patients with renal failure, metabolites may accumulate.
Special Populations and Conditions
Pediatrics: The pharmacokinetic profile of naproxen in children aged 5 to 16 years with arthritis is similar to that in adults although the clearance is generally higher in children than in adults. Pharmacokinetic studies of naproxen were not performed in children less than 5 years of age. Health Canada has not authorized an indication for pediatric use. See 2 CONTRAINDICATIONS.
Geriatric: Studies indicate that although total plasma concentration of naproxen is unchanged, the unbound plasma fraction of naproxen is increased in the elderly, although the unbound fraction is <1% of the total naproxen concentration. Unbound trough naproxen concentrations in elderly subjects have been reported to range from 0.12% to 0.19% of total naproxen concentration, compared with 0.05% to 0.075% in younger subjects.
Hepatic Impairment: Naproxen pharmacokinetics has not been determined in subjects with hepatic insufficiency.
Chronic alcoholic liver disease and probably other diseases with decreased or abnormal plasma proteins (albumin) reduce the total plasma concentration of naproxen, but the plasma concentration of unbound naproxen is increased.
Renal impairment: Given that naproxen and its metabolites are primarily excreted by the kidney, the potential exists for accumulation in the presence of renal insufficiency. Elimination of naproxen is decreased in patients with severe renal impairment. See 2 CONTRAINDICATIONS.
11 STORAGE, STABILITY AND DISPOSAL
Store at room temperature 15°C to 30°C
Keep out of reach and sight of children.
12 SPECIAL HANDLING INSTRUCTIONS
N/A
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper name: Naproxen
Chemical name: (+)-6-methoxy-alpha-methyl-2-naphthalene acetic acid
Molecular formula and molecular mass: C14H14O3; 230.27 g/mol
Structural formula:
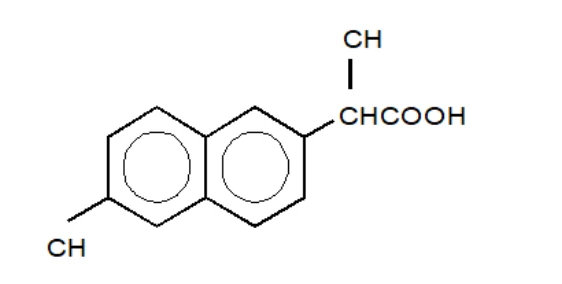
Physicochemical properties: Naproxen is an odourless white crystalline powder with a melting point of 152 to 158°C. It is highly lipid soluble, sparingly soluble in water at low pH, and highly soluble in water at high pH.
14 CLINICAL TRIALS
14.2 Comparative Bioavailability Studies
A randomized, single dose (2 x 250 mg), blinded, 2-way crossover comparative bioavailability study of NAPROXEN (Pro Doc Ltée) and NAPROSYN (Syntex Inc.) was conducted in healthy male volunteers under fasting conditions. A summary of the comparative bioavailability data from 16 volunteers that were included in the statistical analysis are presented in the following table.
Summary Table of the Comparative Bioavailability Data
Naproxen (2 x 250 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUC0-32 (mcg•h/mL) | 907.2 912.6 (11.2) | 926.0 931.0 (10.6) | 98.0 | 95.5 – 100.5 |
AUCI (mcg•h/mL) | 1108.5 1120.2 (15.0) | 1135.9 1145.9 (13.8) | 97.6 | 94.8 – 100.4 |
Cmax (mcg/mL) | 73.5 73.8 (10.0) | 73.1 73.4 (10.4) | 100.6 | 96.5 – 104.8 |
Tmax3 (h) | 2.1 (62.5) | 2.1 (41.6) | ||
T½3 (h) | 14.2 (11.4) | 14.3 (9.5) | ||
1 NAPROXEN (naproxen) tablets, 250 mg (Pro Doc Ltée) 2 NAPROSYN (naproxen) tablets, 250 mg (Syntex, Inc. Canada) 3 Expressed as arithmetic mean (CV %) only | ||||
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Acute Animal Toxicity
The oral LD50 values for naproxen are as follows:
| Hamster | 4110 mg/kg |
|---|---|
| Rats | 543 mg/kg |
| Dogs | >1000 mg/kg |
| Mice | 1234 mg/kg |
Subacute and Chronic Oral Toxicity
In subacute and chronic oral studies with naproxen in a variety of species, the principal pathologic effect was gastrointestinal irritation and ulceration. The lesions seen were predominantly in the small intestine and ranged from hyperemia to perforation and peritonitis.
Nephropathy was seen occasionally in rats, mice and rabbits at high-dose levels of naproxen, but not in rhesus monkeys or miniature pigs. In the affected species, the pathologic changes occurred in the cortex and papilla. Some rats examined 14 days after single oral doses of 230 mg/kg or more of naproxen evidenced necrotic areas of cortical and papillary tissue. Tubular dilation (ectasia) occurred in rabbits dosed orally for 14 days with 200 mg/kg/day or more of naproxen. An examination of unfixed renal tissue from rabbits so treated was conducted and revealed the presence of diffraction patterns similar to that of crystalline naproxen. This suggests that the ectasia observed was physical response to deposition of excreted naproxen within the tubules.
In mice given oral doses of 120 mg/kg/day or more of naproxen for 6 months, the kidneys were characterized by a low but non-dosage-related incidence of cortical sclerosis and papillary tip necrosis. Chronic administration of high doses of naproxen to mice appears to be associated with exacerbation of spontaneous murine nephropathy.
A wide variation in susceptibility to gastrointestinal lesions from administration of naproxen was evident in the various species tested. For example, 30 mg/kg/day was tolerated well by rats for 90 days, but the same dose was ulcerogenic when administered for 6 months. Rhesus monkeys and miniature swine exhibited no significant pathology when dosed with naproxen at 45 mg/kg/day for 30 days. This dose of naproxen was also tolerated by miniature swine without obvious evidence of adverse effects when administered daily for 1 year. In rhesus monkeys doses as high as 120 mg/kg/day administered twice daily for 6 months produced no clinical or histopathological evidence of gastrointestinal irritation although occult blood in the feces occurred more frequently in these animals as compared to controls. In rabbits, the maximum tolerated repeated oral dose is 200 mg/kg/day. Mice tolerated oral daily doses of 240 mg/kg/day for 6 months. In both rabbits and mice, gastrointestinal and renal toxicity was reported at these dose levels. In dogs, on the other hand, 5.0 mg/kg/day approaches the maximum tolerated dose. This peculiar canine susceptibility to gastrointestinal effects of non-steroidal anti-inflammatory agents has also been shown with indomethacin and ibuprofen.
In dogs, naproxen exhibits a considerably longer plasma half-life than it does in rats, guinea pigs, miniature swine, monkeys and man. The same observation has been made with ibuprofen in dogs compared to rats and man. In addition, in the species listed, only the dog excretes significant amounts of administered naproxen in the feces (50%). In the rat, guinea pigs, miniature swine, monkeys and man, 86.94% of the administered drug is excreted in the urine. The suggested enterohepatic circulation of naproxen in the dog (as judged by the fecal excretion) may be a major factor in the susceptibility of the dog to gastrointestinal irritation by this compound.
Pathologic changes in the spleen and mesenteric lymph nodes as well as peritoneal inflammation and adhesions were considered to be clearly secondary to the effects of high doses of naproxen on the gastrointestinal tract. Moderate weight loss of the male secondary sex glands occurred in some studies in naproxen-treated rats and dogs. Histopathologically, the affected glands in some instances exhibited atrophic and/or hypoplastic changes characterized by decreased secretory material. A possible estrogenic action of naproxen as a causative factor seems highly unlikely since in standard bioassay procedures, the drug exhibited no estrogenic activity. Nevertheless, daily doses of naproxen as high as 30 mg/kg administered for 60 days before mating had no effect on fertility and reproductive performance of male rats. These results reflect the physiological integrity of the entire male reproductive apparatus after administration of naproxen throughout the spermatogenic cycle.
Effect on Induced Infections in Rabbits: To determine whether treatment with naproxen affects the ability of animals to respond to bacterial infection, rabbits were inoculated subcutaneously with Diplococcus pneumoniae. For 21 days before bacterial challenge and during a 2-week post-challenge period, the animals were dosed daily by gavage with 2, 10 or 20 mg/kg of naproxen. Clinical condition, morbidity, mortality, gross and histopathologic changes were evaluated. There were no apparent effects of naproxen in altering the response of the animals to bacterial challenge.
Carcinogenicity
Naproxen was administered with food to Sprague-Dawley rats for 24 months at doses of 8, 16 and 24 mg/kg/day. Naproxen was not carcinogenic in rats.
Genotoxicity
Mutagenicity was not seen in Salmonella typhimurium (5 cell lines), Sachharomyces cerevisisae (1 cell line), and mouse lymphoma tests.
Reproductive and Developmental Toxicology
Daily oral administration of 15, 30 or 60 mg/kg of naproxen to female rabbits from 2 weeks before mating until day 20 of pregnancy did not affect fertility, gestation or the numbers of live fetuses.
In a peri- and post-natal study in rats, oral doses of naproxen up to 20 mg/kg administered daily during the last part of pregnancy through weaning did not result in adverse effects in viability of pups, lactation index, sex ratio or weight gain of offspring. However, there was a slight increase in gestation length at the 10 and 20 mg/kg dose levels; and, at the 10 mg/kg dose level, there was a significant increase in stillbirths.
Naproxen at daily oral doses of 12, 36 or 108 mg/kg to female mice from 2 weeks before mating until weaning of the pups did not cause changes in length of gestation, number of live pups born, average pup weight at 0, 4, 7, 14 or 21 days, or sex distribution. The fertility index, gestation index and 4-day viability index were similar for mice from the control and treated groups. The 21-day survival and lactation indexes were decreased for mice from the group fed 108 mg/kg/day of naproxen but not for mice given 12 or 36 mg/kg/day. Most of this change was due to maternal mortality in the high dose group.
Recent evidence suggests that inhibition of prostaglandin synthesis by non-steroidal anti-inflammatory compounds may be related to decreased uterine contractibility. Thus, the onset of labor in a rat model system can be delayed with naproxen administration without causing maternal or fetal deaths in excess of that seen in controls. Since it has been shown that naproxen inhibits prostaglandin synthesis in vitro, it has been suggested that the effects of naproxen on uterine contractility are mediated through that mechanism.
Maternal and fetal deaths seen in naproxen-treated rats were, therefore, apparently related to dystocia rather than to a direct toxic effect of the compound. Naproxen is not unique in this regard since comparable results were obtained in the rat with other commonly used non-steroidal anti-inflammatory agents.
In teratology studies, no skeletal or visceral anomalies or pathologic changes were induced in the fetuses of pregnant rats and rabbits treated during organogenesis with daily oral doses of naproxen up to 20 mg/kg. In these studies, there were also no significant differences from controls in the number of live fetuses, resorptions, fetal weights or ano-genital distances.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. NAPROSYN®, (Naproxen; 375 mg & 500 mg Enteric-Coated Tablets and 750 mg Sustained-Release Tablet), submission control 255330, Product Monograph, Atnahs Pharma UK Limited. (JAN 10, 2022).
- 2. NAPROSYN®, (Naproxen; 250 mg, 375 mg & 500 mg Film-Coated Tablets, 250 mg, 375 mg & 500 mg Enteric-Coated Tablets, 750 mg & 1000 mg Sustained-Release Tablet), 25 mg/mL Suspension, and 500 mg Suppositories), submission control 035645, Product Monograph, Hoffmann-La Roche Limited. (MAY 10, 1995).