


Product Monograph - Nu-Clindamycin
ACTIONS AND CLINICAL PHARMACOLOGY
Clindamycin exerts its antibacterial effect by causing cessation of protein synthesis and also causing a reduction in the rate of synthesis of nucleic acids.
The mechanism of action of clindamycin in combination with primaquine on Pneumocystis carinii is not known.
Absorption
Clindamycin is rapidly and almost completely absorbed from the gastrointestinal tract in man and peak serum levels are seen in about 45 minutes. The average peak serum level following a single 150 mg dose in adults is 2.74 mcg/mL. Therapeutically effective average levels at 6 hours after a 150 mg dose of 0.73 mcg/mL are found.
The absorption of clindamycin is not appreciably affected by food intake. Peak serum levels following a single 250 mg oral dose of clindamycin with the patient in the fasting state were 3.1 mcg/mL at 45 minutes whereas the same dose administered with food gave a peak level of 2.4 mcg/mL. A 250 mg dose administered one hour after food gave a peak level of 2.8 mcg/mL but this peak did not occur until two hours after administration of the medication. A 250 mg dose with the patient in a fasting state and with food administered one hour after the medication resulted in peak levels of 3.1 mcg/mL at 1½ hours.
Excretion
The 48 hour urinary excretion of clindamycin in adults following a single dose of 150 mg represented 10.9% of the administered dose (range 4.8% to 12.8%). These measurements were made by bio-assay and both the percent recovered and the urinary concentration are quite variable. The urinary concentration following a single 50 mg dose of clindamycin in the first 24 hours ranged from 8 to 25 mcg/mL of urine.
Fecal excretion of clindamycin has also been determined. Patients on a three week study when administered 1 gram of clindamycin per day had an average of 283 mcg/gm of stool. Patients on lincomycin 2 grams per day under the same conditions showed 3980 mcg/gm of stool. In single dose studies following administration of 250 mg of clindamycin, only 2.7% of the dose was excreted in the feces in 48-96 hours.
Tissue Penetration
In three patients following the administration of 150 mg of clindamycin serum levels reached 2.25 mcg/mL in 2 hours and declined to 1.5 mcg/mL at 4 hours. During this period antibiotic synovial fluid levels were 1 mcg/mL at 2 hours and remained unchanged for the next and last 2 hours of observation.
Various other body fluids were also assayed for clindamycin and the results of these assays and serum levels at the same time are recorded in the table below.
| Specimen | No. of Specimens | Average Serum Level | Average Fluid Level (mcg/mL) | Tissue Level (mcg/mL) |
Pancreatic fluid (C6-264) Bile (C6-264) Gall Bladder (C6-264) Liver (C6-265) Kidney (C6-265) Bone (C4-390) | 4 19 16 1 1 2 | 1.15 3.35 0.81 42.35 1.50 2.44 | 45.1 52.45 | 4.33 3.80 9.07 9.91 |
Clindamycin does not cross the blood-brain-barrier even in the presence of inflamed meninges.
Comparative Bioavailability
A comparative bioavailability study was performed using healthy human volunteers. The rate and extent of absorption of clindamycin was measured and compared following oral administration of
NU-CLINDAMYCIN or Dalacin® C (1x300 mg) capsules. The results from measured data are summarized as follows:
| Summary Table of the Comparative Bioavailability Data Clindamycin (Dose: 1 x 300 mg) From Measured Data – Under Fasting Conditions | |||
| Parameter | Geometric Mean Arithmetic Mean (CV%) | Ratio of Geometric Means (%)** | |
| NU-CLINDAMYCIN | Dalacin® C† | ||
AUCT (mcg•hr/mL) AUCI (mcg•hr/mL) Cmax (mcg/mL) Tmax (hr)* t1/2 (hr)* | 10.3 10.8 (34) 10.7 11.2 (38) 2.97 3.02 (20) 0.73 (43) 2.44 (31) | 10.8 11.3 (32) 11.1 11.6 (32) 2.87 3.01 (34) 0.89 (38) 2.61 (30) | 96.0 95.8 103.4 - - |
* Arithmetic means (CV%). ** Based on the least squares estimate. † Dalacin®C is manufactured by Pharmacia & Upjohn, and was purchased in Canada. | |||
INDICATIONS AND CLINICAL USE
NU-CLINDAMYCIN (clindamycin hydrochloride) is indicated in the treatment of serious infections due to sensitive anaerobic bacteria, such as bacteroides species, peptostreptococcus, anaerobic streptococci, clostridium species and microaerophilic streptococci.
NU-CLINDAMYCIN is also indicated in serious infections due to sensitive gram-positive organisms (staphylococci, including penicillinase-producing staphylococci, streptococci and pneumococci) when the patient is intolerant of, or the organism resistant to other appropriate antibiotics.
NU-CLINDAMYCIN is indicated for the treatment of the Pneumocystis carinii pneumonia in patients with AIDS. Clindamycin in combination with primaquine may be used in patients who are intolerant to, or fail to respond to conventional therapy.
NU-CLINDAMYCIN is indicated for prophylaxis against alpha-hemolytic (viridans group)
Streptococci before dental, oral and upper respiratory tract surgery.
- a) The prophylaxis of bacterial endocarditis in patients allergic to penicillin with any of the following conditions: congenital cardiac malformations, rheumatic and other acquired valvular dysfunction, prosthetic heart valves, previous history of bacterial endocarditis, hypertrophic cardiomyopathy, surgically constructed systemic-pulmonary shunts, mitral valve prolapse with valvular regurgitation or mitral valve prolapse without regurgitation but associated with thickening and/or redundancy of the valve leaflets.
- b) Patients taking oral penicillin for prevention or recurrence of rheumatic fever should be given another agent such as clindamycin, for prevention of bacterial endocarditis.
CONTRAINDICATIONS
NU-CLINDAMYCIN (clindamycin hydrochloride) is contraindicated in patients previously found to be sensitive to clindamycin or lincomycin or any component of the formulation.
Until further clinical experience is obtained NU-CLINDAMYCIN is not indicated in the newborn
(infants below 30 days of age).
WARNINGS
Clindamycin has been associated with severe antibiotic-associated colitis. Severe colitis may be fatal if left untreated. If significant diarrhea occurs during therapy, this drug should be discontinued or, if necessary, continued only with close observation. It should be noted that diarrhea, colitis, and pseudomembranous colitis have been observed to begin up to one month after discontinuation of medication. A relatively prolonged period of continuing observation is therefore recommended.
The diagnosis of colitis is usually made by recognition of the clinical symptoms. Colitis has a clinical spectrum from mild, watery diarrhea to severe, persistent diarrhea, leukocytosis, fever, severe abdominal cramps which may be associated with the passage of blood and mucus, and which, if allowed to progress, may produce peritonitis, shock and toxic megacolon.
If colitis is suspected, endoscopy is recommended. Endoscopic examination may reveal pseudomembranous colitis. Stool cultures for Clostridium difficile and stool assay for C. difficile toxin may be helpful diagnostically.
Mild cases showing minimal mucosal changes may respond to simple drug discontinuance.
Moderate to severe cases, including those showing ulceration or pseudomembrane formation should be managed with fluid, electrolyte, and protein supplementation as indicated. Corticoid retention enemas and systemic corticoids may be of help in persistent cases, anticholinergic and antiperistaltic agents may worsen the condition. Other causes of colitis should be considered.
Studies indicate a toxin(s) produced by Clostridia (especially Clostridium difficile) is a primary cause of antibiotic-associated colitis and that toxigenic Clostridium is usually sensitive in vitro to vancomycin. When 125 mg to 500 mg of vancomycin were administered orally four times a day for 5 - 10 or more days, there was a rapid observed disappearance of the toxin from faecal samples and a coincidental recovery from the diarrhea.
In patients with G-6-PD deficiency, the combination of clindamycin with primaquine may cause hemolytic reactions; reference should also be made to the primaquine product monograph for other possible risk groups for other hematologic reactions.
PRECAUTIONS
General
Clindamycin hydrochloride should be prescribed with caution in atopic individuals and in individuals with a history of gastrointestinal disease particularly colitis.
Clindamycin hydrochloride does not diffuse adequately into cerebrospinal fluid and thus should not be used in the treatment of meningitis.
The use of antibiotics occasionally results in overgrowth of non-susceptible organisms -particularly yeasts. Should super-infections occur, appropriate measures should be taken as dictated by the clinical situation.
As with all antibiotics, perform culture and sensitivity studies in conjunction with drug therapy.
Periodic liver and kidney function tests and blood counts should be performed during prolonged therapy.
Routine blood examinations should be done during therapy with primaquine to monitor potential hematologic toxicities.
Clindamycin hydrochloride dose modification may not be necessary in patients with renal disease. The serum half-life of clindamycin is increased slightly in patients with markedly reduced renal function.
In patients with moderate to severe liver disease, prolongation of the half-life of clindamycin has been found. However, it was postulated from studies that when given every eight hours, accumulation of clindamycin should rarely occur. Therefore, dosage reduction in liver disease is not generally considered necessary. Periodic liver enzyme determinations should be made when treating patients with severe liver disease.
Use in the Elderly
Experience has demonstrated that antibiotic-associated colitis may occur more frequently and with increased severity among elderly (>60 years) and debilitated patients.
Use in Pregnancy
Reproduction studies have been performed in rats and mice using subcutaneous and oral doses of clindamycin ranging from 20 to 600 mg/kg/day and have revealed no evidence of impaired fertility or harm to the fetus due to clindamycin. In one mouse strain, cleft palates were observed in treated fetuses; this response was not produced in other mouse strains or in other species, and therefore may be a strain specific effect.
Safety for use in pregnancy has not been established.
Clindamycin crosses the placenta in humans. After multiple doses, amniotic fluid concentrations were approximately 30% of maternal blood concentrations. Clindamycin was widely distributed in fetal tissues with the highest concentration found in liver. Clindamycin should not be used in pregnancy unless clearly needed.
Nursing Mothers
Clindamycin has been reported to appear in human breast milk in the range of 0.7 to 3.8 mcg/mL at doses of 150 mg orally to 600 mg intravenously. Because of the potential for adverse reactions in neonates, a decision should be made whether to discontinue nursing or not administer clindamycin after taking into account the importance of the drug to the mother.
Drug Interactions
Antagonism has been demonstrated between clindamycin and erythromycin in vitro. Because of a possible clinical significance, the two drugs should not be administered concurrently.
Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents.
ADVERSE REACTIONS
- 1.
Gastrointestinal - Abdominal pain, nausea, vomiting and diarrhea, colitis (see WARNINGS)
and esophagitis with oral preparations. The onset of pseudomembranous colitis symptoms may occur during or after antimicrobial treatment.
- 2.
Hypersensitivity Reactions – Maculopapular rash and urticaria have been observed during drug therapy. Gereralized mild to moderate morbilliform-like skin rashes are the most frequently reported reactions. Rare instances of erythema multiforme, some resembling
Stevens-Johnson syndrome, have been associated with clindamycin. A few cases of anaphylactoid reactions have been reported.
- 3. Liver – Jaundice and abnormalities in liver function tests have been observed during clindamycin therapy.
- 4. Skin and Mucous Membranes – Pruritus, vaginitis and rare instances of exfoliative and vesiculobullous dermatitis have been reported.
- 5.
Hematopoietic - Transient neutropenia (leukopenia) and eosinophilia have been reported.
Reports of agranulocytosis and thrombocytopenia have been made. No direct etiologic relationship to concurrent clindamycin therapy could be made in any of these instances.
However, in clindamycin/primaquine combination studies, serious hematologic toxicities
(grade III, grade IV neutropenia or anemia, platelet counts < 50 X 109/L, or methemoglobin levels of 15% or greater) have been observed.
- 6. Renal – Although no direct relationship of clindamycin to renal damage has been established, renal dysfunction as evidenced by azotemia, oliguria and/or proteinuria has been observed in rare instances.
- 7. Musculoskeletal – Rare instances of polyarthritis have been reported.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
No cases of overdosage have been reported. It would be expected however, that should overdosage occur, gastrointestinal side effects including abdominal pain, nausea, vomiting and diarrhea might be seen. During clinical trials, one 3-year old child was given 100 mg/kg of clindamycin hydrochloride for five days and showed mild abdominal pain and diarrhea. One 13-year old patient was given 75 mg/kg for five days with no side effects. In both cases laboratory values remained normal.
Overdosage should be treated with simple gastric lavage. Hemodialysis and peritoneal dialysis are not effective means of removing the compound from the blood. No specific antidote is known.
DOSAGE AND ADMINISTRATION
Adults: 150 mg every 6 hours.
Moderately severe infections: 300 mg every 6 hours.
Severe Infections: 450 mg every 6 hours.
Children (over one month of age)
One of the following two dosage ranges should be selected depending on the severity of the infection:
- 1. 8-16 mg/kg/day (4-8 mg/lb/day) divided into 3 or 4 equal doses.
- 2. 16-20 mg/kg/day (8-10 mg/lb/day) divided into 3 or 4 equal doses. Pneumocystis carinii pneumonia in patients with AIDS
NU-CLINDAMYCIN (clindamycin hydrochloride) 300-450 mg may be given orally every 6 hours in combination with 15-30 mg of primaquine for 21 days. If patients should develop serious hematologic adverse effects, reducing the dosage regimen of primaquine and/or NU-
CLINDAMYCIN capsule should be considered.
Absorption of NU-CLINDAMYCIN (clindamycin hydrochloride) is not appreciably modified by ingestion of food and may be taken with meals.
To avoid the possibility of esophageal irritation, NU-CLINDAMYCIN capsules should be taken with a full glass of water.
For prevention of endocarditis
Adults: 300 mg orally 1 hour before procedure; then 150 mg 6 hours after initiaI dose.
Children: 10 mg/kg (not to exceed adult dose) orally 1 hour before procedure; then 5 mg/kg 6 hours after initial dose.
Note: With $-hemolytic streptococcal infections, treatment should continue for at least 10 days to diminish the likelihood of subsequent rheumatic fever or glomerulonephritis.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper/Common Name: Clindamycin hydrochloride
Chemical Name(s): 1) L-threo-"-D-gaIacto-Octopyranoside, methyl 7-chloro-6,7,8-trideoxy-
6-[[(1 -methyl 4-propyl-2-pyrrolidinyl)carbonyl]amino]-1 -thio-, (2S-trans) monohydrochloride
- 2) Methyl 7-chloro-6,7,8-trideoxy-6-(1 -methyl-trans-4-propyl-L-2-pyrrolidinecarboxamino)-1 -thio-L-threo-"-D-gaIacto-octopyranoside monohydrochloride.
Structural Formula: 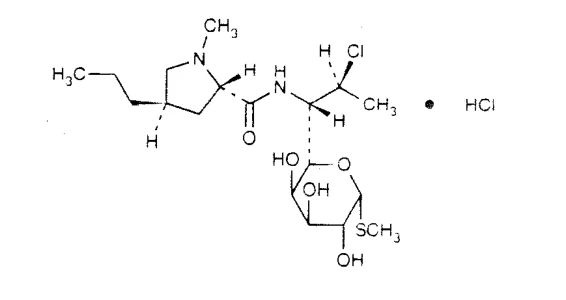
Molecular Formula: C18H33CIN2 O5SqHCl (anhydrous)
Molecular Weight: 461.44 (anhydrous), 479.46 (monohydrate)
Description: Clindamycin hydrochloride is the hydrated hydrochloride salt of clindamycin, a substance produced by the chlorination of lincomycin and is a white to almost white, crystalline powder. It is soluble in water, pyridine, ethanol and DMF (N,N-dimethylformamide). Clindamycin hydrochloride has a pH of 4.4, a pKa of 7.6, a partition coefficient of 185 and a melting point of 141-143°C.
Composition
In addition to the active ingredient, clindamycin hydrochloride, each NU-CLINDAMYCIN capsule contains the non-medicinal ingredient stearic acid. The 150 mg capsule shell contains the non-medicinal ingredients gelatin, titanium dioxide, FD&C Red #40, D&C Red #33, D&C Red #28,
FD&C Blue #1 and FD&C Yellow #5. The 300 mg capsule shell contains the non-medicinal ingredients gelatin, titanium dioxide and FD&C Blue #1.
The edible ink on the capsule shell contains the non-medicinal ingredients shellac glaze-45%
(20% esterified), titanium dioxide, ammonium hydroxide 28%, propylene glycol and simethicone.
Stability and Storage Recommendations
Store at controlled room temperature (15-30°C).
AVAILABILITY OF DOSAGE FORMS
NU-CLINDAMYCIN (Clindamycin Hydrochloride) 150 mg: Each hard gelatin capsule with maroon cap and lavender body, imprinted "150" contains 150 mg of clindamycin base. Supplied in bottles of 100 and 500, and unit dose packages of 100.
NU-CLINDAMYCIN (Clindamycin Hydrochloride) 300 mg: Each hard gelatin capsule with light blue cap and body imprinted "300" contains 300 mg of clindamycin base. Supplied in bottles of
100 and 500, and unit dose packages of 100.
MICROBIOLOGY
In order to assess the significance of in vitro antibiotic activity against bacterial species, it is necessary to compare the organism’s minimum inhibitory concentration (MIC) to the defined susceptibility interpretive breakpoints for the antibiotic. Table 1 identifies the currently-accepted
NCCLS (1990) MIC interpretive breakpoints for clindamycin.
| Table 1: MIC breakpoints for clindamycin (mcg/mL) | |||
| Susceptible | Intermediate | Resistant | |
| Aerobic bacteria | # 0.50 | 1-2 | $ 4 |
| Anaerobic bacteria | # 4.0 | - | $ 8 |
The reported clindamycin MIC90 value (ie., the concentration of clindamycin that inhibits 90% of test isolates) was utilized as the most descriptive measure of clindamycin activity. Where the data from more than one study are summarized, the weighted average MIC90 value was calculated to account for differences in the number of strains in each study.
The in vitro susceptibility of clinical isolates to clindamycin is presented in Table 2 (gram-positive aerobic bacteria), Table 3 (gram-negative aerobic bacteria), Table 4 (gram-positive anaerobic bacteria), Table 5 (gram-negative anaerobic bacteria) and Table 6 (Chlamydia spp and
Mycoplasma spp).
| Table 2: In vitro activity of clindamycin against gram-positive aerobic bacteriaa | |||
| Organism | Nb | MIC90 Rangec | MIC90d |
| Bacillus cereus | 46 | 1 | 1 |
| Corynebacterium diphtheriae | 192 | 0.1 | 0.1 |
| Listeria monocytogenes | 218 | 1-8 | 2.22 |
| Staphylococcus aureus (methicillin-susceptible) | 286 | 0.12-2 | 0.50 |
| Staphylococcus saprophyticus | 57 | 0.12-0.25 | 0.16 |
| Streptococcus agalactia | 59 | #0.06-0.50 | 0.15 |
| Streptococcus bovis | 22 | 0.04 | 0.04 |
| Streptococcus pneumoniae (penicillin-susceptible) | 660 | 0.03-0.25 | 0.23 |
| Streptococcus pyogenes | 141 | 0.13-0.25 | 0.08 |
| Streptococcus spp, Group B | 38 | #0.12-0.25 | 0.15 |
| Streptococcus spp, Group C | 30 | #0.12-0.50 | 0.22 |
| Streptococcus spp, Group G | 34 | 0.06-0.50 | 0.31 |
| Streptococcus spp, viridans Group (penicillin-susceptible) | 67 | #0.06-1.6 | 0.53 |
a Clinical efficacy has not been established for some of these species b N, total number of isolates c Range of reported MIC90 values d MIC90 for single study or weighted average MIC90 for two or more studies | |||
| Table 3: In vitro activity of clindamycin against gram-negative aerobic bacteriaa | |||
| Organism | Nb | MIC90 Rangec | MIC90d |
| Campylobacter jejuni | 449 | 0.39-8 | 1.7 |
| Campylobacter fetus | 41 | 1-1.6 | 1.2 |
| Campylobacter coli | 31 | 0.50 | 0.50 |
| Gardnerella vaginalis | 156 | #0.06-0.39 | 0.3 |
| Helicobacter pylori | 47 | 2-3.1 | 2.6 |
| Neisseria gonorrhoeae ($-lactamase-negative) | 77 | 4 | 4 |
| Neisseria gonorrhoeae ($-lactamase-positive) | 54 | 2 | 2 |
a clinical efficacy has not been established for some of these species b N, total number of isolates c Range of reported MIC90 values d MIC90 for single study or weighted average MIC90 for two or more studies | |||
| Table 4: In vitro activity of clindamycin against gram-positive anaerobic bacteriaa | |||
| Organism | Nb | MIC90 Rangec | MIC90d |
| Actinomyces israelii | 46 | 0.12 | 0.12 |
| Actimomyces spp. | 38 | 0.50-1 | 0.8 |
| Clostridium botulinum | 224 | 4 | 4 |
| Clostridium difficile | 191 | 4->256 | 57.7 |
| Clostridium novyi | 18 | 2 | 2 |
| Clostridium perfringens | 386 | 0.25-8 | 3.4 |
| Clostridium ramosum | 98 | 4-12.5 | 8.3 |
| Eubacterium spp. | 45 | 0.4-2 | 1.1 |
| Lactobacillus spp. | 88 | 0.50-1 | 0.8 |
| Peptostreptococcus anaerobes | 283 | 0.25-0.50 | 0.4 |
| Peptostreptococcus asaccharolyticus | 268 | 0.25-2 | 1.5 |
| Peptostreptococcus magnus | 90 | 2 | 2 |
| Peptostreptococcus prevotii | 87 | 0.12-4 | 2.9 |
| Peptostreptococcus tetradius | 28 | 0.5 | 0.5 |
| Anaerobic gram-positive cocci | 247 | 0.5-1 | 0.9 |
| Propionibacterium acnes | 267 | 0.10-0.25 | 0.2 |
| Propionibacterium spp. | 71 | 0.12-0.20 | 0.16 |
a clinical efficacy has not been established for some of these species b N, total number of isolates c Range of reported MIC90 values d MIC90 for single study or weighted average MIC90 for two or more studies | |||
| Table 5: In vitro activity of clindamycin against gram-negative anaerobic bacteriaa | |||
| Organism | Nb | MIC90 Rangec | MIC90d |
| Bacteroides fragilis group | 4,284 | 0.5-8 | 2.45 |
| Bacteroides fragilis | 2,002 | #0.20-4 | 2.22 |
| Bacteroides melaninogenicus | 224 | #0.03-0.50 | 0.07 |
| Bacteroides spp. | 141 | #0.06-0.50 | 0.31 |
| Bacteroides bivius | 155 | #0.03-#0.05 | #0.11 |
| Bacteroides disiens | 33 | #0.03-#0.06 | #0.05 |
| Fusobacterium spp. | 330 | #0.10-2 | 0.85 |
| Mobiluncus mulieris | 10 | 0.06 | 0.06 |
| Mobiluncus curtisii | 12 | 0.12 | 0.12 |
| Veillonella spp. | 38 | 0.06-0.25 | 0.20 |
a clinical efficacy has not been established for some of these species b N, total number of isolates c Range of reported MIC90 values d MIC90 for single study or weighted average MIC90 for two or more studies | |||
Clindamycin has demonstrated in vitro activity against Chlamydia trachomatis and Mycoplasma spp (see Table 6). For Chlamydia trachomatis, the MIC90 for clindamycin is reached at 2.3 mcg/mL; in vitro synergism with gentamycin has also been demonstrated.
| Table 6: In vitro activity of clindamycin against Chlamydia spp and Mycoplasma sppa | |||
| Organism | Nb | MIC90 Rangec | MIC90d |
| Chlamydia trachomatis | 84 | 0.5-5.9 | 2.3 |
| Mycoplasma hominis | 106 | 0.25-0.8 | 0.58 |
| Mycoplasma pneumoniae | 9 | 4 | 4 |
a clinical efficacy has not been established for some of these species b N, total number of isolates c Range of reported MIC90 values d MIC90 for single study or weighted average MIC90 for two or more studies | |||
The in vitro activity of clindamycin in combination with primaquine has not been determined.
Development of resistance to clindamycin by staphlococci is slow and stepwise rather than rapid and streptomycin-like. Clindamycin, like lincomycin, participates in the dissociated cross-resistance phenomenon with erythromycin. Clindamycin is not cross-resistant with penicillin, ampicillin, tetracycline or streptomycin. It is, however, cross-resistant with lincomycin.
Resistance to clindamycin may occur by one of several mechanisms. Resistance does not appear to be caused by reduced drug uptake but rather is generally due to alterations in the bacterial target site (50S ribosomal subunit). Resistance can result from either changes in a ribosomal protein at the receptor site or a change in the 23S ribosomal RNA by methylation of adenine. Rare isolates of staphylococci and some veterinary isolates of streptococci may enzymatically inactivate clindamycin by adenylation. Plasmid-mediated transferable resistance to clindamycin (and erythromycin) in B. fragilis was reported in 1979. Despite the existence of multiple resistance mechanisms, the reported incidence of clindamycin resistance in the B. fragilis group has remained relatively low (averaging 5.3% from 1970-1987 in over 7,600 isolates).
Susceptibility of isolates to clindamycin should be assessed by individual MIC determinations.
PHARMACOLOGY
Three large multiple dose tolerance studies were conducted in normal volunteers.
One group of 216 volunteers took 1 gram per day or 2 grams per day of clindamycin for 4 weeks.
The most frequent side effect noted was diarrhea in some volunteers, particularly at the 2 gram per day dose which is more than 3 times the recommended daily dose. With the exception of one patient who developed infectious hepatitis during the study, laboratory tests showed no significant aberrations considered drug related. Occasional patients developed elevated serum transaminase and serum alkaline phosphatase.
A second group of 150 volunteers was similarly treated and laboratory determinations were essentially normal. Audiograms were performed before, during and up to 90 days after treatment and showed no drug-related changes.
A third group of 172 volunteers was evaluated in a comparison of lincomycin 500 mg q.i.d., ampicillin 250 mg q.i.d., clindamycin 150 mg q.i.d., and placebo. Subjects receiving ampicillin showed a peak incidence of moderate to mild diarrhea second only to lincomycin and greater than clindamycin during the first week of therapy, then demonstrated a drop in the incidence to placebo levels or below during the second and third week. Meanwhile, the incidence of diarrhea in both the lincomycin and the clindamycin groups remained slightly above that reported for the placebo group during the second and third weeks of therapy. One patient on lincomycin and one on clindamycin developed a rash. No drug related laboratory test abnormalities were noted.
Five volunteers were evaluated before and after treatment with clindamycin 500 mg q.i.d., for 10 days with reference to true or pseudo-cholinesterase levels. No abnormalities in these levels were noted.
TOXICOLOGY
Animal
The results of acute toxicity studies are shown in Table 7:
| Table 7: Animal LD50 Results | ||
| Species | Route | LD50 (mg/kg) |
| Adult Mouse | i.p. | 262 |
| Adult Mouse | i.v. | 143 |
| Adult Rat | Oral | 2714 |
| Adult Rat | s.c. | 2618 |
| Newborn Rat | s.c. | 245 |
The following subacute and chronic animal toxicology was performed:
5 Day Oral Tolerance Study in Rats
500 mg/kg was administered to rats with no drug related toxicity noted except that all rats developed diarrhea at this dose level.
5 Day Oral Tolerance Study in the Dog
Doses of 113 mg/kg and 500 mg/kg were administered. The higher dose was vomited 1-2 hours after administration but otherwise no abnormalities of a drug-related nature were noted.
6 Month Subacute Oral Toxicity in the Rat
Clindamycin, at doses of 30,100 and 300 mg/kg, was given to groups of 20 rats daily for 6 months. Data obtained after one month were normal. Similarly, data at the end of 6 months showed no drug related effects. A fourth group of 20 rats received a dose of 600 mg/kg for 3 months and also showed the drug to be well tolerated by male and female rats without any drug related effects.
1 Month Subacute Oral Toxicity in the Dog
Clindamycin, at doses of 30,100 and 300 mg/kg, was given to 3 groups of 6 dogs with a comparable group of 6 dogs as a control. All dogs were healthy and all dose levels well tolerated.
Fluctuations in the serum glutamic pyruvic transaminase values were seen in the 300 mg/kg group after 2 weeks therapy. Less fluctuation was seen in the SGOT levels and other tests of hepatic function did not reflect the adaptive metabolic change which these elevated transaminase values are believed to show. Two dogs in each group were sacrificed and no drug related lesions were found upon complete necropsy and microscopic observations on these dogs.
1 Year Chronic Oral Toxicity in the Rat
Doses of 0, 30,100 and 300 mg/kg were administered daily to rats for one year and 600 mg/kg for
6 months. As expected, mortality did occur due to coincidental disease and the group at 600 mg/kg had a higher mortality rate although no definitive drug related findings were noted.
1 Year Chronic Oral Toxicity in the Dog
Dogs were administered clindamycin at doses of 0, 30,100 and 300 mg/kg for 1 year. Some dose related elevations of serum glutamic pyruvic transaminase values were seen during the 7th to 9th month of this study, but periodic liver biopsies examined by light and electron microscopy did not disclose any hepatic cell damage. All other data noted no drug related changes. Teratogenic and Reproductive Studies in the Rat
Teratologic evaluation of 20-day foetuses was made and no evidence of teratogenic effect was noted. Treated rat dams gave birth to normal litters and no evidence was obtained that clindamycin affected the fecundity of the dam or the development of the offspring.
Teratogenic and Reproductive Studies in the Mouse
Clindamycin, in doses of 20, 50 and 200 mg/kg, was administered to pregnant mice from day 6 through day 15 of gestation. At the 200 mg/kg level there was pronounced expected toxicity associated with a 40% mortality. Similarly, at this toxic level there was increased foetal loss. Litter size, litter weight and mean pup weight were significantly reduced. At the 200 mg/kg level there was an increased incidence of major malformations which is thought to be due to malnutrition of the dam as a result of this toxic dose of the drug.
BIBLIOGRAPHY
- 1. Argoudelis AD, Coats JH, Mason DJ, Sebek OK. Microbial transormations of lincomycin, clindamycin and related antibiotics. Antimicrob Agents Chemother 1968.
- 2.
Bartlett JG, Onderdonk AB, Cisneros RL. Clindamycin-associated colitis in hamsters:
protection with vancomycin. Gastroenterology 1977;73:772-6.
- 3. Bartlett JG, Chang T, Onderdonk AB. Comparison of five regimens for treatment of experimental clindamycin-associated colitis. J Infect Dis 1978;138:81-6.
- 4.
Bartlet JG, Chang T, Taylor NS, Onderdonk AB. Colitis induced by Clostridium difficile. Rev
Infect Dis 1979;1:370-8.
- 5.
Birkenmeyer RD. Influence of halogen substitution on the antibacterial activity of lincomycin.
Abstract #37, 5th lnterscience conference on antimicrobial agents and chemotherapy, October 1965, Washington, DC.
- 6. Black JR, Feinberg J, Murphy RL, Fass RJ, Finkelstein D, Akil B, et al. Clindamycin and primaquine therapy for mild-to-moderate episodes of Pneumocystis carinii pneumonia in patients with AIDS: AIDS Clinical Trials Group 044. Clin lnf Dis 1994;18:905-13.
- 7.
Brodasky TF et al. The characterization and thin-layer chromatographic quantitation of the human metabolite of 7-deoxy-7 (S) chlorolincomycin (U-21, 251 F). J Antibiot 1968;21:327-
33.
- 8.
Browne RA, Fekety R, Silva J, Boyd Dl, Work CO, Abrams GD. The protective effect of vancomycin on clindamycin-induced colitis in hamsters. John Hopkins Med J 1977;141 :183-
92.
- 9.
Burdon DW, Brown JD, George RH, Arabi Y, Alexander-Williams J, Keighley MRB.
Pseudomembranous colitis caused by Clostridia. N Engl J Med 1978;299:48.
- 10.
Burdon DW, Brown JD, Young DJ, Arabi Y, Shinagawa N, Alexander-Williams J, Keighley
MRB. Antibiotic susceptibility of Clostridium difficile. J Antimicrob Chemother 1979;5:307-10.
- 11. Fekety R. Prevention and treatment of antibiotic-associated colitis. Microbiology 1979:276-9.
- 12. Garrison DW, DeHaan RM, Lawson JB. Comparison of in vitro antibacterial activities of 7-chloro-7deoxylincomycin, lincomycin and erythromycin. Antimicrob Agents Chemother 1967:168-71.
- 13. George WL, Kirby BD, Sutter VL, Finegold SM. Antimicrobial susceptibility of Clostridium difticile. Microbiology 1979:267-71.
- 14.
Hogan LB, Holloway WJ. An evaluation of 7-chlorolincomycin. Antibicrobial Agents and
Chemotherapy 1968.
- 15. Humphrey CD, Condon CW, Cantey JR, Pittman FE. Partial purification of a toxin found in hamsters with antibiotic-associated colitis: reversible binding of the toxin by cholestyramine. Gastroenterology 1979;76:468-76.
- 16.
Katz L, LaMont JT, Trier JS, Sonnenblick EB, Rothman SW, Broitman SA, Rieth S.
Experimental clindamycin-associated colitis in rabbits: evidence for toxin-mediated mucosal damage. Gastroenterology 1978;74:246-52.
- 17. Kay R, Dubois RE. Clindamycin/primaquine therapy and secondary prophylaxis against pneumocystis carinii pneumonia in patients with AIDS. South Med J 1990; 3 (4): 403-4.
- 18.
Keighley MRB, Burdon DW, Arabi Y, Alexander-Williams J, Thompson H, Young D, Johnson
M, Bentley S, George RH, Mogg GAG. Randomized controlled trial of vancomycin for pseudomembranous colitis and postoperative diarrhea. Br Med J 1978;2:1667-9.
- 19. LaMont JT, Sonnenblick EB, Rothman S. Role of clostridial toxin in the pathogenesis of clindamycin colitis in rabbits. Gastroenterology 1979; 76:356-61.
- 20. Lattanzi WE, Krosnick MY, Hurwitz S, Goldstein P, Krassner L. The treatment of $-hemolytic streptococcal throat infections with clindamycin. Int Med Digest I 969;4:29-31.
- 21. Lewis C. Antiplasmodial activity of 7-halogenated lincomycins. J Parasitol 1965;54:169-70.
- 22. Lewis C. The antiplasmodial activity of halogenated lincomycin analogs in plasmodium berghi infected mice. Antimicrob Agents Chemother 1967:537-42.
- 23. Lewis C. Stem KF, Mason DJ. Antibacterial and pharmacological properties of clindamycin, a new semi-synthetic antibiotic. Antimicrob Agents Chemother 1968.
- 24.
Magerlein BJ, Birkenmeyer RO, Kagan F. Chemical modification of lincomycin. Antimicrob
Agents Chemother 1966;727-36.
- 25. McGehee RJ, Barrett FF, Finland M. Resistance of Staphylococcus aureus to lincomycin, clinimycin and erythromycin. Antimicrob Agents Chemother 1968:392-97.
- 26.
Roeser J. Inhibition of resistance factor transfer by clinimycin and its analogues. Antimicrob
Agents Chemother 1968:41-7.
- 27. Safrin S, Finkelstein DM, Feinberg J, Frame P, Simpson G, Wu A, et al. Comparison of three regimens for treatment of mild to moderate Pneumocystis carinii pneumonia in patients with AIDS. Ann Intern Med 1996;124(9):792-802.
- 28.
Santos RJ, Romansky MJ, Evantash HM. 7-chlorolincomycin, laboratory and clinical studies.
Antimicrob Agents Chemother 1968.
- 29. Tedesco F, Markham R, Gurwith M, Christie D. Bartlett JG. Oral vancomycin for antibiotic-associated pseudomembranous colitis. Lancet 1978;2:226-8.
- 30.
Toma E. Clindamycin/primaquine for treatment of pneumocystis carninii pneumonia in AlDS.
Eur J Clin Microbiol Infect Dis 1991; 10:210-3.
- 31. Toma E, Fournier S, Dumont M, Bolduc P, Deschamps H. Clindamycin/primaquine versus trimethoprim-sulfamethoxazole as primary therapy for Pneumocystis carinii pneumonia in AIDS: A randomized, double-blind pilot trial. Clin lnf Dis 1993;17:178-84.
- 32. Wagner JG, Novak E, Patel NC, Chidester CG, Lummis WL. Absorption, excretion and half-life of clinimycin in normal adult males. Am J Med Sci 1968; 1:25-37.