


Product Monograph - Paclitaxel for Injection (Pfizer Canada)
SUMMARY PRODUCT INFORMATION
| Route of Administration | Dosage Form / Strength | Clinically Relevant Nonmedicinal Ingredients |
| Intravenous | Solution for Injection, 6 mg/mL | Anhydrous citric acid Absolute Alcohol (also referred to as Ethanol) PEG 35 castor oil (Cremophor® EL) For a complete listing see Dosage Forms, Composition and Packaging section. |
INDICATIONS AND CLINICAL USE
Paclitaxel for Injection is indicated, alone or in combination, for:
- Treatment of carcinoma of the ovary, breast, or lung.
Ovarian Carcinoma
- First-line treatment in combination with other chemotherapeutic agents.
- Second-line treatment of metastatic carcinoma of the ovary after failure of standard therapy.
Breast Carcinoma
- Adjuvant treatment of node-positive breast cancer administered sequentially to standard combination therapy. In the clinical trial, there was an overall favorable effect on disease-free and overall survival in the total population of patients with receptor-positive and receptor-negative tumors, but the benefit has been specifically demonstrated by available data (median follow-up 30 months) only in the patients with estrogen and progesterone receptor-negative tumors (see SCIENTIFIC INFORMATION - Clinical Trials).
- Second-line treatment of metastatic carcinoma of the breast after failure of standard therapy.
Lung Carcinoma
- First-line treatment of advanced non-small cell lung cancer.
CONTRAINDICATIONS
- Patients who have a history of severe hypersensitivity reactions to paclitaxel or other drugs formulated in Cremophor® EL (polyethoxylated castor oil).
- Patients with severe baseline neutropenia (< 1,500 cells/mm3).
WARNINGS AND PRECAUTIONS
General
Paclitaxel should be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents.
Contact of the undiluted concentrate with plasticized polyvinyl chloride (PVC) equipment or devices used to prepare solutions for infusion is not recommended. In order to minimize patient exposure to the plasticizer DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted Paclitaxel for Injection solutions should preferably be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets.
Carcinogenesis and Mutagenesis
See section TOXICOLOGY under SCIENTIFIC INFORMATION.
Second Primary Malignancies: Acute myeloid leukemia and myelodysplastic syndrome have been reported in post-market reports.
Cardiovascular
Hypotension, hypertension and bradycardia have been observed during paclitaxel administration; patients are usually asymptomatic and generally do not require treatment. In severe cases, paclitaxel infusions may need to be interrupted or discontinued at the discretion of the treating physician. Frequent monitoring of vital signs, particularly during the first hour of paclitaxel infusion, is recommended. Continuous cardiac monitoring is not required except for patients who develop serious conduction abnormalities (see ADVERSE REACTIONS).
Serious Warnings and Precautions
- Should only be administered under the supervision of a physician experienced in the use of cancer chemotherapeutic agents (see INDICATIONS AND CLINICAL USE).
- Paclitaxel for Injection should be administered as diluted infusion.
- Patients should be pre-treated with corticosteroids, antihistamines, and H2 antagonist (see Sensitivity/Resistance section below).
- Should not be administered to patients with baseline neutrophil counts of less than 1,500 cells/mm3 (see Hematologic section below).
Severe cardiac conduction abnormalities have been reported in < 1% of patients during paclitaxel therapy. If patients develop significant conduction abnormalities during administration, appropriate therapy should be administered and continuous electrocardiographic monitoring should be performed during subsequent therapy with Paclitaxel for Injection.
Driving/Operating Machinery
Since Paclitaxel for Injection contains ethanol (absolute alcohol), consideration should be given to the possibility of CNS and other effects.
Gastrointestinal
Severe mucositis has been reported which requires dose reduction (see ADVERSE REACTIONS, DOSAGE AND ADMINISTRATION).
Pseudomembranous colitis has been reported in patients who have not been concomitantly treated with antibiotics. This reaction should be considered in the differential diagnosis of cases of severe or persistent diarrhea occurring during or shortly after treatment with paclitaxel (see ADVERSE REACTIONS).
Endocrine and Metabolism
Tumor lysis syndrome has been reported in in post-market reports.
Hematologic
Paclitaxel for Injection should not be administered to patients with baseline neutrophil counts of less than 1,500 cells/mm3 (see CONTRAINDICATIONS). Bone marrow suppression (primarily neutropenia) is dose and schedule dependent and is the dose-limiting toxicity within a regimen. Neutrophil nadirs occurred at a median of 11 days. In order to monitor the occurrence of myelotoxicity, it is recommended that frequent peripheral blood cell counts be performed on all patients receiving Paclitaxel for Injection. Patients should not be re-treated with subsequent cycles of Paclitaxel for Injection until neutrophils recover to a level > 1,500 cells/mm3 and platelets recover to a level > 100,000 cells/mm3. In the case of severe neutropenia (< 500 cells/mm3) during a course of Paclitaxel for Injection therapy, a 20% reduction in dose for subsequent courses of therapy is recommended (see DOSAGE AND ADMINISTRATION).
Hepatic/Biliary/Pancreatic
There is evidence that the toxicity of paclitaxel is enhanced in patients with elevated liver enzymes. Caution should be exercised when administering Paclitaxel for Injection to patients with moderate to severe hepatic impairment and dose adjustments should be considered (see ADVERSE REACTIONS).
Injection Site Reaction
Injection site reactions, including reactions secondary to extravasation, were usually mild and consisted of erythema, tenderness, skin discoloration, or swelling at the injection site. These reactions have been observed more frequently with the 24-hour infusion than with the three-hour infusion. Recurrence of skin reactions at a site of previous extravasation following administration of paclitaxel at a different site, i.e., “recall”, has been reported rarely.
Rare reports of more severe events such as phlebitis, cellulitis, induration, skin exfoliation, necrosis and fibrosis have been received as part of the continuing surveillance of paclitaxel safety. In some cases the onset of the injection site reaction either occurred during a prolonged infusion or was delayed by a week to ten days.
A specific treatment for extravasation reactions is unknown at this time. Given the possibility of extravasation, it is advisable to closely monitor the infusion site for possible infiltration during drug administration.
Neurologic
Although the occurrence of peripheral neuropathy is frequent, the development of severe symptomatology is unusual. A dose reduction of 20% is recommended for all subsequent courses of Paclitaxel for Injection for severe neuropathy (see ADVERSE REACTIONS, DOSAGE AND ADMINISTRATION).
When a combination of cisplatin and paclitaxel regimens is used as first-line treatment in women with advanced ovarian cancer, it has been reported that a three hour infusion of paclitaxel in combination with cisplatin may result in a greater incidence of severe neurotoxicity than paclitaxel followed by cisplatin. Paclitaxel when it is given in combination with a platinum compound, e.g. cisplatin, should be given before the platinum compound.
Paclitaxel for Injection contains ethanol (absolute alcohol), 396 mg/mL; consideration should be given to possible CNS and other effects of ethanol (absolute alcohol). Children may be more sensitive than the adults to the effects of ethanol (absolute alcohol); see Special Populations - Pediatrics.
Ophthalmologic
There have been reports of reduced visual acuity due to cystoid macular edema (CME) during treatment with Paclitaxel as well as with other taxanes (see Post-Market Adverse Drug Reactions). Most reports of CME have resolved after cessation of the taxane treatment. Patients with visual impairment during Paclitaxel treatment should seek a prompt and complete ophthalmologic examination. Paclitaxel should be discontinued if a CME diagnosis is confirmed.
Sensitivity/Resistance
Paclitaxel for Injection should be administered as a diluted infusion. Patients receiving Paclitaxel for Injection should be pre-treated with corticosteroids, antihistamines, and H2 antagonists (such as dexamethasone, diphenhydramine and cimetidine or ranitidine) to minimize hypersensitivity reactions (see DOSAGE AND ADMINISTRATION).
Anaphylaxis and severe hypersensitivity reactions characterized by dyspnea and hypotension requiring treatment, angioedema, or generalized urticaria have occurred in approximately 2% of patients receiving Paclitaxel for Injection. These reactions are probably histamine-mediated. Rare fatal reactions have occurred in patients despite pre-treatment. In case of a severe hypersensitivity reaction, paclitaxel infusion should be discontinued immediately and the patient should not be rechallenged with the drug (see ADVERSE REACTIONS).
Patients with a history of severe hypersensitivity reactions to products containing Cremophor® EL should not be treated with Paclitaxel for Injection (see CONTRAINDICATIONS). Minor symptoms such as flushing, skin reactions, dyspnea, hypotension or tachycardia do not require interruption of therapy. However, severe reactions, such as hypotension requiring treatment, dyspnea requiring bronchodilators, angioedema or generalized urticaria require immediate discontinuation of Paclitaxel for Injection and aggressive symptomatic therapy.
Sexual Health
Fertility: Male patients should seek advice regarding cryoconservation of sperm prior to treatment with paclitaxel because of the possibility of infertility.
Special Populations
Pregnant Women: Paclitaxel for Injection may cause fetal harm when administered to a pregnant woman. Paclitaxel has been shown to be embryotoxic and fetotoxic in rabbits and to decrease fertility in rats. There are no studies in pregnant women. Women of childbearing potential should be advised to avoid becoming pregnant during therapy with Paclitaxel for Injection. If Paclitaxel for Injection is used during pregnancy, or if the patient becomes pregnant while receiving this drug, the patient should be apprised of the potential hazard.
Nursing Women: It is not known whether paclitaxel is excreted in human milk. Breast feeding should be discontinued for the duration of paclitaxel therapy.
Pediatrics: The safety and effectiveness of paclitaxel in pediatric patients have not been established. There have been reports of central nervous system (CNS) toxicity (rarely associated with death) in a clinical trial in pediatric patients in which paclitaxel was infused intravenously over three hours at doses ranging from 350 mg/m2 to 420 mg/m2 . The toxicity is most likely attributable to the high dose of the ethanol component of the paclitaxel vehicle given over a short infusion time. The use of concomitant antihistamines may intensify this effect. Although a direct effect of the paclitaxel itself cannot be discounted, the high doses used in this study (over twice the recommended adult dosage) must be considered in assessing the safety of paclitaxel for use in this population.
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The frequency and severity of adverse events are generally similar between patients receiving paclitaxel for the treatment of ovarian, breast or non-small cell lung carcinoma. The most frequent significant undesirable effect of paclitaxel was bone marrow suppression. Neutropenia was dose and schedule dependent and was generally rapidly reversible.
Fever was frequent (12% of all treatment courses). Infectious episodes occurred in 30% of all patients and 9% of all courses; these episodes were fatal in 1% of all patients, and included sepsis, pneumonia and peritonitis. Twenty percent of the patients experienced a drop in their platelet count below 100,000 cells/mm3 at least once while on treatment. Anemia (Hb < 11 g/dL) was observed in 78 % of all patients and was severe (Hb < 8 g/dL) in 16% of the cases. No consistent relationship between dose or schedule and the frequency of anemia was observed.
Hypersensitivity reactions were observed in 20% of all courses and in 41% of all patients. These reactions were severe in less than 2% of the patients and 1% of the courses and occurred generally within the first hour of paclitaxel infusion. The most frequent symptoms observed during these severe reactions were dyspnea, flushing, chest pain and tachycardia.
Hypotension, during the first three hours of infusion, occurred in 12% of all patients and 3% of all courses administered. Peripheral neuropathy was observed in 60% of all patients (3% severe) and in 52% (2% severe) of the patients without pre-existing neuropathy. Peripheral neuropathy was the cause of paclitaxel discontinuation in 1% of all patients.
Sixty percent of all patients treated in single-agent trials experienced arthralgia/myalgia; 8% experienced severe symptoms. Alopecia was observed in almost all patients. Nausea/vomiting, diarrhea and mucositis were reported by 52%, 38% and 31% of all patients, respectively. These manifestations were usually mild to moderate. Among patients with normal baseline liver function 7%, 22% and 19% had elevations in bilirubin, alkaline phosphate and AST (SGOT), respectively.
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
The incidences of adverse reactions in the table that follows are derived from ten clinical trials in carcinoma of the ovary and of the breast involving 812 patients treated with single-agent paclitaxel at doses ranging from 135-300 mg/m2/day and schedules of three or 24 hours. Data from a subset of 181 patients treated at the recommended dose of 175 mg/m2 and a three-hour infusion schedule is also included in the table.
| Table 1 - Incidences of adverse reactions from clinical trials in carcinoma of the ovary and of the breast involving patients treated with single-agent paclitaxel at doses ranging from 135-300 mg/m2/day and schedules of three or 24 hours. |
135-300 mg/m2 % of Patients N=812 | 175 mg/m2 % of Patients N=181 | |
|---|---|---|
Bone Marrow Neutropenia < 2,000/mm3 < 500/mm3 Leukopenia < 4,000/mm3 < 1,000/mm3 Thrombocytopenia < 100,000/mm3 | 90 52 90 17 20 | 87 27 86 4 6 |
135-300 mg/m2 % of Patients N=812 | 175 mg/m2 % of Patients N=181 | |
|---|---|---|
< 50,000/mm3 Anemia < 11 g/dL < 8 g/dL Infections Bleeding Red Cell Transfusions Red Cell Transfusions (normal baseline) Platelet Transfusions | 7 78 16 30 14 25 12 2 | 1 62 6 18 9 13 6 0 |
Hypersensitivity Reactions All Severe | 41 2 | 40 2 |
Cardiovascular Bradycardia (first three hours of infusion) Hypotension (first three hours of infusion) Severe events | 3 12 1 | 3 11 2 |
Abnormal ECG All Patients Patients with normal baseline | 23 14 | 13 8 |
Peripheral Neuropathy Any symptoms Severe symptoms | 60 3 | 64 4 |
Myalgia/Arthralgia Any symptoms Severe symptoms | 60 8 | 54 12 |
Gastrointestinal Nausea and vomiting Diarrhea Mucositis | 52 38 31 | 44 25 20 |
| Alopecia | 87 | 93 |
Hepatic (Patients with normal baseline) Bilirubin elevations Alkaline phosphatase elevations AST elevations | 7 22 19 | 4 18 18 |
| Injection site reactions | 13 | 4 |
Safety referring to a large randomized trial of paclitaxel (135 mg/m2 over 24 hours) / cisplatin (75 mg/m2) versus cyclophosphamide/cisplatin, including 410 patients (196 receiving paclitaxel), has been evaluated. The combination of paclitaxel with platinum agents has not resulted in any clinically relevant changes to the safety profile of the drug when used at the recommended dosage.
Safety data were collected for 3,121 patients in the Phase III adjuvant breast carcinoma study. The adverse event profile for the patients who received paclitaxel subsequent to cyclophosphamide and doxorubicin was consistent with that seen in the pooled analysis of data from 812 patients treated with single-agent paclitaxel in 10 clinical studies.
Summary of Three-hour Infusion Data at a Dose of 175 mg/m2
Unless otherwise stated, the following safety data relate to 62 patients with ovarian cancer and 119 patients with breast cancer treated at a dose of 175 mg/m2 and a three-hour infusion schedule, in Phase III clinical trials. All patients were pre-medicated to minimize hypersensitivity reactions. Data from these clinical trials demonstrate that paclitaxel given at this dose and schedule is well tolerated. Bone marrow suppression and peripheral neuropathy were the principle dose-related adverse effects associated with paclitaxel. Compared to 24-hour infusion schedules, neutropenia was less common when paclitaxel was given as a three-hour infusion. Neutropenia was generally rapidly reversible and did not worsen with cumulative exposure. The frequency of neurologic symptoms increases with repeated exposure.
None of the observed toxicities were influenced by age.
Adverse Experiences by Body System
Unless otherwise noted, the following discussion refers to the overall safety database of 812 patients with solid tumors treated with single-agent paclitaxel in 10 clinical studies. Toxicities that occurred with greater severity or frequency in previously untreated patients with ovarian carcinoma or NSCLC who received paclitaxel in combination with cisplatin or in patients with breast cancer who received paclitaxel after doxorubicin/cyclophosphamide in the adjuvant setting, and that occurred with a difference that was clinically significant in these populations are also described. In addition, rare events have been reported from postmarketing experience or from other clinical studies.
The frequency and severity of adverse events have been generally similar for all patients receiving Paclitaxel for Injection.
Hematologic
The most frequent significant undesirable effect of paclitaxel was bone marrow suppression. Neutropenia was dose and schedule dependent and was generally rapidly reversible. Severe neutropenia (< 500 cells/mm3) occurred in 27% of patients treated at a dose of 175 mg/m2, but was not associated with febrile episodes. Only 1% of patients experienced severe neutropenia for seven days or more. Neutropenia was not more frequent or severe in patients who received prior radiation therapy, nor did it appear to be affected by treatment duration or cumulative exposure.
When paclitaxel was administered to patients with ovarian carcinoma at a dose of 175 mg/m2/3 hours in combination with cisplatin versus the control arm of cyclophosphamide plus cisplatin, the incidences of severe neutropenia and of febrile neutropenia were similar in the paclitaxel plus cisplatin arm and in the control arm.
When paclitaxel was administered in combination with cisplatin to patients with advanced NSCLC in the Eastern Cooperative Oncology Group (ECOG) study, the incidence of neutropenia (Grade IV) was 74% (paclitaxel 135 mg/m2/24 hours plus cisplatin) and 65% (paclitaxel 250 mg/m2/24 hours plus cisplatin and G-CSF) compared with 55% in patients who received cisplatin/etoposide. Considerably less Grade IV neutropenia was observed in the
European Organization for Research and Treatment of Cancer (EORTC) (28%) and CA139-208 (45%) studies for paclitaxel 175 mg/m2/3 hours plus cisplatin (without G-CSF).
Fever was frequent (12% of all treatment courses). Infectious episodes occurred in 30% of all patients and 9% of all courses; these episodes were fatal in 1% of all patients, and included sepsis, pneumonia and peritonitis. In the Phase III second-line ovarian study, infectious episodes were reported in 20% of the patients given 135 mg/m2 and 26% of the patients given 175 mg/m2 by a three-hour infusion. Urinary tract infections and upper respiratory tract infections were the most frequently reported infectious complications. The use of supportive therapy, including G-CSF, is recommended for patients who have experienced severe neutropenia (see DOSAGE AND ADMINISTRATION).
Twenty percent of the patients experienced a drop in their platelet count below 100,000 cells/mm3 at least once while on treatment; 7% had a platelet count < 50,000 cells/mm3 at the time of their worst nadir. Bleeding episodes were reported in 4% of all courses and by 14% of all patients, but most of the hemorrhagic episodes were localized and the frequency of these events was unrelated to the paclitaxel dose and schedule. In the Phase III second-line ovarian cancer study, bleeding episodes were reported in 10% of the patients who received study medication; however, none of the patients treated with the three-hour infusion received platelet transfusions. In the adjuvant breast carcinoma trial, the incidence of severe thrombocytopenia and platelet transfusions increased with higher doses of doxorubicin.
Anemia (Hb < 11 g/dL) was observed in 78% of all patients and was severe (Hb < 8 g/dL) in 16% of the cases. No consistent relationship between dose or schedule and the frequency of anemia was observed. Among all patients with normal baseline hemoglobin, 69% became anemic on study but only 7% had severe anemia. Red cell transfusions were required in 25% of all patients and in 12% of those with normal baseline hemoglobin levels.
Hypersensitivity Reactions (HSR)
All patients received pre-medication prior to paclitaxel (see WARNINGS AND PRECAUTIONS). The frequency and severity of HSR were not affected by the dose or schedule of paclitaxel administration. In the Phase III second-line ovarian study, the three-hour infusion was not associated with a greater increase in HSR when compared to the 24-hour infusion. Hypersensitivity reactions were observed in 20% of all courses and in 41% of all patients. These reactions were severe in less than 2% of the patients and 1% of the courses. No severe reactions were observed after course three and severe symptoms occurred generally within the first hour of paclitaxel infusion. The most frequent symptoms observed during these severe reactions were dyspnea, flushing, chest pain and tachycardia.
The minor hypersensitivity reactions consisted mostly of flushing (28%), rash (12%), hypotension (4%), dyspnea (2%), tachycardia (2%) and hypertension (1%). The frequency of hypersensitivity reactions remained relatively stable during the entire treatment period.
Cardiovascular
Hypotension, during the first three hours of infusion, occurred in 12% of all patients and 3% of all courses administered. Bradycardia, during the first three hours of infusion, occurred in 3% of all patients and 1% of all courses. In the Phase III second-line ovarian study, neither dose nor schedule had an effect on the frequency of hypotension and bradycardia. These vital sign changes most often caused no symptoms and required neither specific therapy nor treatment discontinuation. The frequency of hypotension and bradycardia were not influenced by prior anthracycline therapy.
Significant cardiovascular events possibly related to single-agent paclitaxel occurred in approximately 1% of all patients. These events included syncope, rhythm abnormalities, hypertension and venous thrombosis. One of the patients with syncope treated with paclitaxel at 175 mg/m2 over 24 hours had progressive hypotension and died. The arrhythmias included asymptomatic ventricular tachycardia, bigeminy and complete AV block requiring pacemaker placement. The incidence of Grade III or greater cardiovascular events was 13% (paclitaxel 135 mg/m2/24 hours plus cisplatin), 12% (paclitaxel 250 mg/m2/24 hours plus cisplatin and G-CSF), and 6% (paclitaxel 175 mg/m2/3 hours plus cisplatin) when paclitaxel followed by cisplatin was administered to patients with advanced NSCLC; there was a similar incidence in the non-paclitaxel control arms. The apparent increase in these cardiovascular events in patients with NSCLC compared to patients with breast or ovarian cancer is possibly related to the difference in cardiovascular risk factors among patients with lung cancer.
Electrocardiogram (ECG) abnormalities were common among patients at baseline. ECG abnormalities on study did not usually result in symptoms, were not dose-limiting, and required no intervention. ECG abnormalities were noted in 23% of all patients. Among patients with a normal ECG prior to study entry, 14% of all patients developed an abnormal tracing while on study. The most frequently reported ECG modifications were non-specific repolarization abnormalities, sinus bradycardia, sinus tachycardia and premature beats. Among patients with normal ECG at baseline, prior therapy with anthracyclines did not influence the frequency of ECG abnormalities.
Cases of myocardial infarction have reported rarely. Congestive heart failure has been reported typically in patients who have received other chemotherapy, notably anthracyclines (see DRUG INTERACTIONS).
Neurologic
The frequency and severity of neurologic manifestations were influenced by prior and concomitant therapy with cisplatin. In general, the frequency and severity of neurologic manifestations were dose-dependent in patients receiving single-agent paclitaxel. Peripheral neuropathy was observed in 60% of all patients (3% severe) and in 52% (2% severe) of the patients without pre-existing neuropathy.
The frequency of peripheral neuropathy increased with cumulative dose. Neurologic symptoms were observed in 27% of the patients after the first course of treatment and in 34-51% from course two to 10. Peripheral neuropathy was the cause of paclitaxel discontinuation in 1% of all patients. Sensory symptoms have usually improved or resolved within several months of Paclitaxel for Injection discontinuation. The incidence of neurologic symptoms did not increase in the subset of patients previously treated with cisplatin. Pre-existing neuropathies resulting from prior therapies are not a contraindication for paclitaxel therapy. In the Intergroup first-line ovarian carcinoma study, the regimen with paclitaxel 175 mg/m2 by three-hour infusion followed by cisplatin 75 mg/m2 resulted in greater incidence and severity of neurotoxicity (reported as neuromotor or neurosensory events) than the regimen containing cyclophosphamide 750 mg/m2 followed by cisplatin 75 mg/m2, 87% (21% severe) versus 52% (2% severe), respectively. In the GOG first-line ovarian carcinoma study, the regimen with paclitaxel (135 mg/m2 over 24 hours) followed by cisplatin (75 mg/m2) resulted in an incidence of neurotoxicity (reported as peripheral neuropathy) that was similar to the regimen containing cyclophosphamide 750 mg/m2 followed by cisplatin 75 mg/m2, 25% (3% severe) versus 20% (0% severe), respectively. Cross-study comparison of neurotoxicity in Intergroup and GOG trials suggests that when paclitaxel is given in combinations with cisplatin 75 mg/m2, the incidence of severe neurotoxicity is more common at a paclitaxel dose of 175 mg/m2 given by three-hour infusion (21%) than at a dose of 135 mg/m2 given by 24-hour infusion (3%). In patients with NSCLC, administration of paclitaxel followed by cisplatin resulted in greater incidence of severe neurotoxicity compared to the incidence in patients with ovarian or breast cancer treated with single-agent paclitaxel. Severe neurosensory symptoms were noted in 13% of NSCLC patients receiving paclitaxel 135 mg/m2 by 24-hour infusion followed by cisplatin 75 mg/m2 and 8% of NSCLC patients receiving cisplatin/etoposide.
Arthralgia/myalgia
There was no consistent relationship between dose or schedule of paclitaxel and the frequency or severity of arthralgia/myalgia. Sixty percent of all patients treated in single-agent trials experienced arthralgia/myalgia; 8% experienced severe symptoms. The symptoms were usually transient, occurred two or three days after paclitaxel administration, and resolved within a few days. The frequency and severity of musculoskeletal symptoms remained unchanged throughout the treatment period.
Alopecia
Alopecia was observed in almost all patients.
Gastrointestinal
Nausea/vomiting, diarrhea and mucositis were reported by 52%, 38% and 31% of all patients, respectively. These manifestations were usually mild to moderate. Mucositis was schedule dependent and occurred more frequently with the 24-hour than with the three-hour infusion.
In the first-line Phase III ovarian carcinoma study, the incidence of nausea and vomiting when paclitaxel was administered in combination with cisplatin appeared to be greater compared with the database for single-agent paclitaxel in ovarian and breast carcinoma. In the same study, diarrhea of any grade was reported more frequently (16%) compared to the control arm (8%) (p = 0.008), but there was no difference for severe diarrhea.
Hepatic
No relationship was observed between liver function abnormalities and either dose or schedule of paclitaxel administration. Among patients with normal baseline liver function 7%, 22% and 19% had elevations in bilirubin, alkaline phosphatase and AST (SGOT), respectively. There is no evidence that paclitaxel when given as a three-hour infusion to patients with mildly abnormal liver function causes exacerbation of abnormal liver function. Prolonged exposure to paclitaxel was not associated with cumulative hepatic toxicity.
Injection Site Reactions
Injection site reactions, including reactions secondary to extravasation, were usually mild and consisted of erythema, tenderness, skin discoloration, or swelling at the injection site. These reactions have been observed more frequently with the 24-hour infusion than with the three-hour infusion.
A specific treatment for extravasation reactions is unknown at this time. Given the possibility of extravasation, it is advisable to closely monitor the infusion site for possible infiltration during drug administration.
Other
Transient skin changes due to paclitaxel-related hypersensitivity reactions have been observed, but no other skin toxicities were significantly associated with paclitaxel administration. Nail changes (changes in pigmentation or discoloration of nail bed) were uncommon (2%). Edema was reported in 21% of all patients (17% of those without baseline edema); only 1% had severe edema and none of these patients required treatment discontinuation. Edema was most commonly focal and disease-related. Edema was observed in 5% of all courses for patients with normal baseline and did not increase with time on study.
In the Phase III trial of paclitaxel 135 mg/m2 over 24 hours in combination with cisplatin as first-line therapy of ovarian cancer, asthenia was reported in 17% of the patients, significantly greater than the 10% incidence observed in the control arm of cyclophosphamide/cisplatin.
Less Common Clinical Trial Adverse Drug Reactions (< 1%)
Cardiovascular: Cases of myocardial infarction have been reported rarely.
Gastrointestinal: Rare reports of neutropenic enterocolitis (typhlitis), despite the co-administration of G-CSF, were observed in patients treated with paclitaxel alone and in combination with other chemotherapeutic agents.
Injection Site Reactions: Recurrence of skin reactions at a site of previous extravasation following administration of paclitaxel at a different site, i.e., “recall”, has been reported rarely.
Neurologic: Other than peripheral neuropathy, serious neurologic events following paclitaxel administration have been rare (< 1%) and have included grand mal seizures, ataxia and encephalopathy.
Respiratory: Rare reports of radiation pneumonitis have been received in patients receiving concurrent radiotherapy.
Post-Market Adverse Drug Reactions
Carcinogenesis and Mutagenesis, Second Primary Malignancies: Acute myeloid leukemia and myelodysplastic syndrome have been reported.
Cardiovascular: Rare reports of atrial fibrillation and supraventricular tachycardia have been received as part of the continuing surveillance of paclitaxel safety. Cardiomyopathy has been reported in very rare cases.
Endocrine and Metabolism: Tumor lysis syndrome has been reported.
Gastrointestinal: Rare reports of intestinal obstruction, intestinal perforation, pancreatitis, ischemic colitis, and dehydration have been received as part of the continuing surveillance of paclitaxel safety.
General disorders and administration site conditions: Reports of asthenia and malaise have been received as part of the continuing surveillance of paclitaxel safety.
Hepatic: Rare reports of hepatic necrosis and hepatic encephalopathy leading to death have been received as part of the continuing surveillance of paclitaxel safety.
Hypersensitivity Reactions (HSR): Rare reports of chills and reports of back pain in association with hypersensitivity reactions have been received as part of the continuing surveillance of paclitaxel safety.
Infection and infestations: Pseudomembranous colitis has been reported.
Injection Site Reactions: Rare reports of more severe events such as phlebitis, cellulitis, induration, skin exfoliation, necrosis and fibrosis have been received as part of the continuing surveillance of paclitaxel safety. In some cases the onset of the injection site reaction either occurred during a prolonged infusion or was delayed by a week to ten days.
Musculoskeletal and connective tissue: Systemic lupus erythematosus and scleroderma have been reported.
Neurologic: Rare reports of autonomic neuropathy resulting in paralytic ileus and motor neuropathy with resultant minor distal weakness have been received as part of the continuing surveillance of paclitaxel safety. Optic nerve and/or visual disturbances (scintillating scotoma) have also been reported, particularly in patients who have received higher doses than those recommended. These effects generally have been reversible. However, rare reports in the literature of abnormal visual evoked potentials in patients have suggested persistent optic nerve damage. Post-marketing reports of ototoxicity (hearing loss and tinnitus) have been received.
Ophthalmologic: There have been reports of reduced visual acuity due to cystoid macular edema (CME) during treatment with paclitaxel as well as with other taxanes (see WARNINGS AND PRECAUTIONS). Based on a number of literature cases, an association between CME and Paclitaxel is considered to be reasonably well established. Features specific to this clinical entity include an absence of vascular leakage with no other precipitating factors, and positive dechallenge in most cases.
Respiratory, thoracic and mediastinal disorders: Rare cases of respiratory failure, interstitial pneumonia, pulmonary embolism and lung fibrosis have been reported as post-marketing adverse drug reactions.
Skin and subcutaneous tissue disorders: Rare reports of skin abnormalities related to radiation recall as well as reports of maculopapular rash, pruritus, Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiforme and dermatitis exfoliative have been received as part of the continuing surveillance of paclitaxel safety.
DRUG INTERACTIONS
Serious Drug Interactions
|
Overview
Cisplatin
In a Phase I trial in which paclitaxel was administered as a 24-hour infusion and cisplatin was administered as a 1 mg/min infusion, myelosuppression was more profound when paclitaxel was given after cisplatin than with the alternate sequence (i.e. paclitaxel before cisplatin). When paclitaxel is given before cisplatin, the safety profile of paclitaxel is consistent with that reported for single-agent use. Pharmacokinetic data from these patients demonstrated a decrease in paclitaxel clearance of approximately 33% when paclitaxel was administered following cisplatin. Therefore, Paclitaxel for Injection should be given before cisplatin when used in combination.
Cimetidine
The effect of cimetidine pre-medication on the metabolism of paclitaxel has been investigated; the clearance of paclitaxel was not affected by cimetidine pre-treatment.
Substrates, Inducers, Inhibitors of Cytochrome P450 2C8 and 3A4
The metabolism of paclitaxel is catalyzed by cytochrome P450 isoenzymes CYP2C8 and CYP3A4. Caution should be exercised when administering Paclitaxel for Injection concomitantly with known substrates, inducers or inhibitors of the cytochrome P450 isoenzymes CYP2C8 and CYP3A4. In vitro, the metabolism of paclitaxel to 6α-hydroxypaclitaxel was inhibited by a number of agents (ketoconazole, verapamil, diazepam, quinidine, dexamethasone, cyclosporine, teniposide, etoposide, vincristine, deferasirox, trimethoprim, and St. John’s wort), but the concentrations used exceeded those found in vivo following normal therapeutic doses. Testosterone, 17α-ethinyl estradiol, retinoic acid, montelukast and quercetin, a specific inhibitor of CYP2C8, also inhibited the formation of 6α-hydroxypaclitaxel in vitro. The pharmacokinetics of paclitaxel may also be altered in vivo as a result of interactions with compounds that are substrates, inducers, or inhibitors of CYP2C8 and/or CYP3A4.
Potential interactions between paclitaxel, a substrate of CYP3A4, and protease inhibitors (ritonavir, saquinavir, indinavir, and nelfinavir), which are substrates and/or inhibitors of CYP3A4, have not been evaluated in clinical trials. Caution and close monitoring of liver function is required; further, no unapproved (e.g., investigational) protease inhibitor should be administered with Paclitaxel for Injection.
Doxorubicin
Sequence effects characterized by more profound neutropenic and stomatitis episodes, have been observed with combination use of paclitaxel and doxorubicin when paclitaxel was administered BEFORE doxorubicin and using longer than recommended infusion times (paclitaxel administered over 24 hours; doxorubicin administered over 48 hours). Plasma levels of doxorubicin (and its active metabolite doxorubicinol) may be increased when Paclitaxel for Injection and doxorubicin are used in combination. However, data from a trial using bolus doxorubicin and three-hour paclitaxel infusion found no sequence effects on the pattern of toxicity.
Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 2 - Established or Potential Drug-Drug Interactions
| Paclitaxel | Ref | Effect | Clinical comment |
| Cisplatin | CT | ↓ paclitaxel clearance when paclitaxel was administered following cisplatin. Patients treated with paclitaxel and cisplatin may have an increased risk of renal failure as compared to cisplatin alone in gynecological cancers. | Paclitaxel for Injection should be given before cisplatin when used in combination. |
| Cimetidine | CT | No effect | The clearance of paclitaxel was not affected by cimetidine pre-treatment. |
| Ketoconazole, verapamil, diazepam, quinidine, dexamethasone, cyclosporine, teniposide, etoposide, vincristine, testosterone, 17α-ethinyl estradiol, retinoic acid, montelukast, quercetin, deferasirox and trimethoprim. | T | Metabolism of paclitaxel to 6α-hydroxypaclitaxel was inhibited | Caution should be exercised when administering Paclitaxel for Injection concomitantly with known substrates, inducers or inhibitors of the cytochrome P450 isoenzymes CYP2C8 and CYP3A4. |
| Doxorubicin | T | More profound neutropenic and stomatitis episodes | Plasma levels of doxorubicin (and its active metabolite doxorubicinol) may be increased when Paclitaxel for Injection and doxorubicin are used in combination. |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
Drug-Food Interactions
Interactions with food have not been established.
Drug-Herb Interactions
Established or potential interactions with herbal products include St-John’s Wort.
Drug-Laboratory Interactions
Interactions with laboratory tests have not been established.
DOSAGE AND ADMINISTRATION
Recommended Dose and Dosage Adjustment
Patients who experience severe neutropenia (neutrophil count <0.5 x 10⁹/L for a minimum of 7 days) or severe peripheral neuropathy or severe mucositis should receive a dose reduced by 20% (see WARNINGS AND PRECAUTIONS).
Metastatic carcinoma of the ovary
The administration of Paclitaxel for Injection at a dose of 175 mg/m2 over three hours in combination with cisplatin 75 mg/m2 every three weeks is recommended for the primary treatment of patients with advanced carcinoma of the ovary. Paclitaxel for Injection should be given before cisplatin when used in combination.
In patients previously treated with chemotherapy, the recommended regimen is 175 mg/m2 administered intravenously over three hours every three weeks.
Carcinoma of the breast
For the adjuvant treatment of node-positive breast cancer, the recommended regimen is Paclitaxel for Injection, at a dose of 175 mg/m2 intravenously over three hours every three weeks for four courses administered sequentially to standard combination therapy. After failure of initial chemotherapy for metastatic disease or relapse within six months of adjuvant chemotherapy, Paclitaxel for Injection at a dose of 175 mg/m2 administered intravenously over three hours every three weeks has been shown to be effective.
Non-small cell lung carcinoma
The recommended regimen, given every three weeks, is Paclitaxel for Injection administered intravenously over three hours at a dose of 175 mg/m2 followed by cisplatin.
Single courses of Paclitaxel for Injection should not be repeated until the neutrophil count is at least 1,500 cells/mm3 and the platelet count is at least 100,000 cells/mm3. Patients who experience severe neutropenia (neutrophil < 500 cells/mm3) or severe peripheral neuropathy during Paclitaxel for Injection therapy should have the dosage reduced by 20% for subsequent courses of Paclitaxel for Injection.
Administration
Note: Undiluted concentrate should not come in contact with plasticized PVC equipment. In order to minimize patients exposure to the plasticizer DEHP [di-(2-ethylhexyl)phthalate], which may be leached from PVC infusion bags or sets, diluted
Paclitaxel for Injection solutions should preferably be stored in bottles (glass, polypropylene) or plastic bags (polypropylene, polyolefin) and administered through polyethylene-lined administration sets.
Paclitaxel for Injection should be administered through an in-line filter with a microporous membrane not greater than 0.22 microns. Use of filter devices such as IVEX-2® filters which incorporate short inlet and outlet PVC-coated tubing has not resulted in significant leaching of DEHP.
All patients should be pre-medicated prior to Paclitaxel for Injection administration in order to reduce the risk of severe hypersensitivity reactions. Such pre-medication may consist of dexamethasone 20 mg orally (or its equivalent) approximately 12 and six hours before Paclitaxel for Injection, diphenhydramine 50 mg IV (or its equivalent), 30 to 60 minutes prior to Paclitaxel for Injection, and cimetidine (300 mg) or ranitidine (50 mg) IV 30 to 60 minutes before Paclitaxel for Injection.
Preparation Precautions
Paclitaxel for Injection is a cytotoxic anticancer drug and, as with other potentially toxic compounds, caution should be exercised in handling Paclitaxel for Injection. The use of gloves is recommended. Following topical exposure, tingling, burning, redness have been observed. If Paclitaxel for Injection solution contacts the skin, wash the skin immediately and thoroughly with soap and water.
If Paclitaxel for Injection contacts mucous membranes, the membranes should be flushed thoroughly with water. Upon inhalation, dyspnea, chest pain, burning eyes, sore throat and nausea have been reported. Given the possibility of extravasation, it is advisable to closely monitor the infusion site for possible infiltration during drug administration (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS).
Reconstitution:
Parenteral Products:
| Amount of finished product (6mg/mL) | Common Diluents | Amount of diluent 1 (Theoretical fill) | Packaging system | Final Concentration | ||||
| 5 mL | 0.9% Sodium Chloride Injection or 5% Dextrose Injection | 100 mL | non-PVC infusion bags (ie. Polyolefin bag) or Glass Bottles | 0.3 mg/mL | ||||
| 20 mL | 1.2 mg/mL | |||||||
1 Prior to the addition of drug, calculate the appropriate volume of diluent to be removed from packaging system to take into account the overage of diluent volume in the packaging system and the amount of drug to be added.
Paclitaxel for Injection must be diluted prior to infusion. Paclitaxel for Injection should be diluted in 0.9% Sodium Chloride Injection, 5% Dextrose Injection, 5% Dextrose and 0.9% Sodium Chloride Injection, or 5% Dextrose in Ringer's Injection to a final concentration of 0.3 to 1.2 mg/mL.
The solutions are physically and chemically stable for up to 27 hours at ambient temperature (15 - 25°C) and room lighting conditions; infusions should be completed within this time frame. There have been rare reports of precipitation with longer than the recommended three-hour infusion schedules. Excessive agitation, vibration or shaking may induce precipitation and should be avoided. Infusion sets should be flushed thoroughly with a compatible diluent before use.
Upon preparation, solutions may show haziness, which is attributed to the formulation vehicle. No significant loss in potency has been noted following simulated delivery of the solution through IV tubing containing an in-line (0.22 micron) filter.
Data collected for the presence of the extractable plasticizer DEHP [di-(2-ethylhexyl)phthalate] show that levels increase with time and concentration when dilutions are prepared in PVC containers. Consequently, the use of plasticized PVC containers and administration sets is not recommended. Paclitaxel for Injection solutions should be prepared and stored in glass, polypropylene, or polyolefin containers. Non-PVC containing administration sets, such as those which are polyethylene-lined, should be used.
Devices with spikes should not be used with vials of Paclitaxel for Injection since they can cause the stopper to collapse resulting in loss of sterile integrity of Paclitaxel for Injection solution.
OVERDOSAGE
There is no known antidote for paclitaxel overdosage. The primary anticipated complications of overdosage would consist of bone marrow suppression, peripheral neurotoxicity and mucositis. Overdoses in pediatric patients may be associated with acute ethanol toxicity (see WARNINGS AND PRECAUTIONS).
| For management of a suspected drug overdose, contact your regional Poison Control Centre immediately. |
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Paclitaxel is an antimicrotubule antineoplastic agent. It promotes microtubule assembly by enhancing the polymerisation of tubulin, the protein subunit of spindle microtubules, even in the absence of the mediators normally required for microtubule assembly (e.g. guanosine triphosphate [GTP]), thereby inducing the formation of stable, nonfunctional microtubules. While the precise mechanism of action of the drug is not completely known, paclitaxel disrupts the dynamic equilibrium within the microtubule system and blocks cells in the late G2 phase and M phase of the cell cycle, inhibiting cell replication and impairing function of nervous tissue.
In vitro, paclitaxel exhibits cytotoxic activity against a wide variety of both human and rodent tumor cell lines including leukemia, non-small cell lung carcinoma, small cell lung carcinoma, colon carcinoma, CNS carcinoma, melanoma, renal carcinoma, ovarian carcinoma and breast carcinoma (see DETAILED PHARMACOLOGY).
Pharmacokinetics
Table 3 - Summary of paclitaxel’s pharmacokinetic parameters in patients given doses of 135 and 175 mg/m2 as three hour and 24 hours infusions.
| t½ (h) | Clearance | Volume of distribution | |
|---|---|---|---|
| Single dose mean | 3.0 to 52.7 hours | 11.6 to 24.0 L/h/m2 | 198 to 688 L/m2 |
Absorption: The pharmacokinetics of paclitaxel have been evaluated over a wide range of doses, up to 300 mg/m2, and infusion schedules ranging from three to 24 hours. Following intravenous administration of paclitaxel, the drug exhibited a biphasic decline in plasma concentrations. The initial rapid decline represents distribution to the peripheral compartment and elimination of the drug. The later phase is due, in part, to a relatively slow efflux of paclitaxel from the peripheral compartment. In patients treated with doses of 135 and 175 mg/m2 given as three and 24 hour infusions, mean terminal half-life has ranged from 3.0 to 52.7 hours, and total body clearance has ranged from 11.6 to 24.0 L/h/m2. Mean steady state volume of distribution has ranged from 198 to 688 L/m2, indicating extensive extravascular distribution and/or tissue binding.
Following three hour infusions of 175 mg/m2, mean terminal half-life was estimated to be 9.9 hours; mean total body clearance was 12.4 L/h/m2.
Variability in systemic paclitaxel exposure, as measured by AUC0-∞ for successive treatment courses was minimal; there was no evidence of accumulation of paclitaxel with multiple treatment courses.
The pharmacokinetics of paclitaxel have been shown to be non-linear. There is a disproportionately large increase in Cmax and AUC with increasing dose, accompanied by an apparent dose-related decrease in total body clearance. These findings are most readily observed in patients in whom high plasma concentrations of paclitaxel are achieved. Saturable processes in distribution and elimination/metabolism may account for these findings.
Distribution: In vitro studies of binding to human serum proteins, using paclitaxel concentrations ranging from 0.1 to 50 mcg/mL, indicated that on average 89% of drug is bound; the presence of cimetidine, ranitidine, dexamethasone, or diphenhydramine did not affect protein binding of paclitaxel.
Metabolism: In vitro studies with human liver microsomes and tissue slices showed that paclitaxel was metabolized primarily to 6α-hydroxypaclitaxel by the cytochrome P450 isozyme
CYP2C8; and to two minor metabolites, 3-p-hydroxypaclitaxel and 6α, 3'-p-dihydroxypaclitaxel by CYP3A4. In vitro, the metabolism of paclitaxel to 6α-hydroxypaclitaxel was inhibited by a number of agents (see DRUG INTERACTIONS). The effect of renal or hepatic dysfunction on the disposition of paclitaxel has not been investigated.
Excretion: The disposition of paclitaxel has not been fully elucidated in humans. After intravenous administration of paclitaxel, mean values for cumulative urinary recovery of unchanged drug ranged from 1.3 to 12.7% of the dose, indicating extensive non-renal clearance. In five patients administered a 225 or 250 mg/m2 dose of radiolabeled paclitaxel as a three-hour infusion, 14% of the radioactivity was recovered in the urine and 71 % was excreted in the feces in 120 hours. Total recovery of radioactivity ranged from 56% to 101 % of the dose. Paclitaxel represented a mean of 5% of the administered radioactivity recovered in the feces while metabolites, primarily 6α-hydroxypaclitaxel, accounted for the balance.
STORAGE AND STABILITY
Paclitaxel for Injection should be stored at room temperature (15 -25°C). Retain in the original package and protect from light and freezing. Once punctured, the 16.7 mL vial of Paclitaxel for Injection is stable for 28 days at room temperature (15 -25°C). The presentation is labeled as a multi-dose vial.
Solutions for infusion prepared as recommended may be stored at room temperature (15 - 25°C) only if necessary. However, the infusion should be initiated within 24 hours of reconstitution.
If unopened vials are refrigerated, a precipitate may form which redissolves with little or no agitation upon reaching room temperature. Product quality is not affected. If the solution remains cloudy or if an insoluble precipitate is noted, the vial should be discarded.
As with all parenteral drug products, injections/intravenous ad-mixtures should be inspected visually for clarity, particulate matter, precipitate, discoloration and leakage prior to administration whenever solution and container permit. Solutions showing haziness, particulate matter, precipitate, discoloration or leakage should not be used. Discard unused portion.
SPECIAL HANDLING INSTRUCTIONS
Contact of undiluted Paclitaxel for Injection with plasticized PVC equipment or devices used to prepare solutions for infusion is not recommended (see DOSAGE AND ADMINISTRATION).
Prior to infusion, Paclitaxel for Injection should be diluted in 0.9% Sodium Chloride Injection, 5% Dextrose Injection, 5% Dextrose and 0.9% Sodium Chloride Injection or 5% Dextrose in Ringer's Injection to a final concentration of 0.3 to 1.2 mg/mL.
As with all parenteral drug products, intravenous admixtures should be inspected visually for clarity, particulate matter, precipitate, discoloration and leakage prior to administration, whenever solution and container permit.
Paclitaxel for Injection should be administered through an in-line filter with a microporous membrane not greater than 0.22 microns.
Preparation of Paclitaxel for Injection should be done in a vertical laminar flow hood (Biological Safety Cabinet - Class II).
Personnel preparing Paclitaxel for Injection should wear PVC gloves, safety glasses, disposable gowns and masks.
All needles, syringes, vials and other materials which have come in contact with Paclitaxel for Injection should be segregated and incinerated at 1000°C or more. Sealed containers may explode. Intact vials should be returned to the Manufacturer for destruction. Proper precautions should be taken in packaging these materials for transport.
Personnel regularly involved in the preparation and handling of Paclitaxel for Injection should have bi-annual blood examinations.
DOSAGE FORMS, COMPOSITION AND PACKAGING
Paclitaxel for Injection is available in multi-dose vials of 16.7 mL containing 100 mg of paclitaxel, at a concentration of 6 mg/mL. The presentation is available in a single-pack carton.
Each mL of Paclitaxel for Injection contains paclitaxel 6 mg, Cremophor® EL (polyethoxylated castor oil) 527 mg, Citric Acid (anhydrous) 2 mg and Absolute Alcohol 46.5% v/v.
PART II: SCIENTIFIC INFORMATION
PHARMACEUTICAL INFORMATION
Drug Substance
| Proper name: | Paclitaxel |
| Chemical name: | 5β,20-epoxy-1,2α,4,7β,10β,13α-hexahydroxytax-11-en-9-one 4, 10-diacetate 2-benzoate 13-ester with (2R, 3S)-N-benzoyl-3-phenylisoserine Or [2aR-[2aα, 4β, 4aβ, 6β, 9α(αR*,βS*), 11α, 12α, 12aα, 12bα]]-β-(Benzoylamino)-α- hydroxybenzenepropanoic acid 6, 12b-bis (acetyloxy)-12-(benzoyloxy)-2a, 3, 4, 4a, 5, 6, 9, 10, 11, 12, 12a, 12b-dodecahydro-4,-11-dihydroxy-4a, 8, 13, 13-tetramethyl-5-oxo-7, 11-methano-1H-cyclodeca-[3, 4] benz [1,2-b]oxet-9-yl ester |
| Structural formula: | 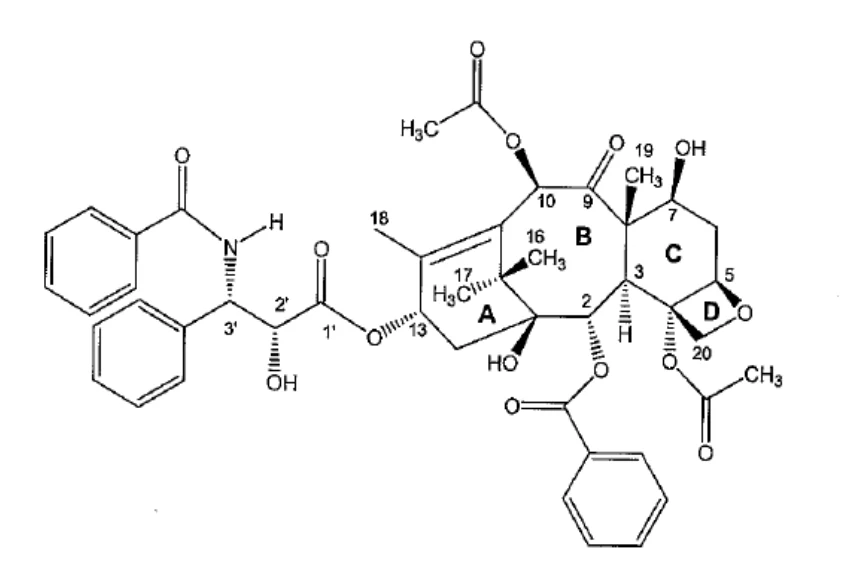 |
| Molecular formula: | C47H51NO14 |
| Molecular mass: | 853.9 |
| Physicochemical properties: | Paclitaxel is a white powder with a melting point of 214 - 230°C. Paclitaxel is not soluble in water but is soluble to varying degrees in organic solvents. |
CLINICAL TRIALS
Clinical Trials
Ovarian Carcinoma
| Study Design | Treatments / Doses | No. of Pts. | Population | Endpoints/Conclusion |
First-Line data: Phase III multicenter, randomized, controlled trial conducted by GOG, comparing therapy with paclitaxel (P) in combination with cisplatin [c] to cyclophosphamide (AC) in combination with cisplatin [c] |
| 410 | Stage III of IV disease (> 1 cm residual disease after staging laparotomy or distant metastases) with no prior chemo-therapy | Patients treated with P in combination with cisplatin has significantly longer time to progression (median 16.6 vs. 13.0 months, p=0.0008) and nearly a year longer median survival time (p=0.0002) compared with standard therapy. |
Second-Line data: Phase III multicenter, bifactorial, randomized trial comparing two dosage regimens of paclitaxel (P) irrespective of the schedules and two schedules irrespective of dose. |
| 407 | Patients (pts) who have failed initial or subsequent chemo-therapy for metastatic carcinoma of the ovary. | Pts receiving the 175 mg/m2 dose had a response rate (RR) similar to that for those receiving the 135 mg/m2 dose: 18% vs. 14% (p=0.28). No difference in RR was detected when comparing the 3-hr with the 24-hr infusion: 15% vs. 17% (p=0.50). Pts receiving the 175 mg/m2 dose of P had a longer time to progression (TTP) than those receiving the 135 mg/m2 dose: median 4.2 vs. 3.1 months (p=0.03). The median TTP for pts receiving the 3-hr vs. the 24-hr infusion were 4.0 months vs. 3.7 months, respectively. Median survival was 11.6 months in pts receiving the 175 mg/m2 dose of P and 11.0 months in pts receiving the 135 mg/m2 dose (p=0.92). Median survival was 11.7 months for pts receiving the 3-hr infusion of P and 11.2 months for pts receiving the 24-hr infusion (p=0.91). |
First-Line data: The adverse event profile for patients receiving paclitaxel in combination with cisplatin was consistent with that seen in previous clinical studies (see ADVERSE REACTIONS).
Second-Line data: In addition to the Phase III trial described above, data from five Phase I and II clinical studies as well as an interim analysis of data from more than 300 patients enrolled in a treatment referral center program were used in support of the use of paclitaxel in patients who have failed initial or subsequent chemotherapy for metastatic carcinoma of the ovary. Paclitaxel remained active in patients who had developed resistance to platinum-containing therapy (defined as tumor progression while on, or tumor relapse within six months from completion of, a platinum containing regimen) with response rates of 14% in the Phase III study and 31 % in the Phase I and II clinical studies. The adverse event profile in this Phase III study was consistent with that seen in previous clinical studies (see ADVERSE REACTIONS).
The results of this randomized study support the use of paclitaxel at doses of 135 to 175 mg/m2 administered by a three-hour intravenous infusion. The same doses administered by 24-hour infusion were more toxic.
Breast Carcinoma
| Study Design | Treatments / Doses | No. of Pts. | Population | Endpoints/Conclusion |
Adjuvant Breast Carcinoma Study: Phase III multicenter, 3X2 factorial, randomized trial, conducted by CALGB, ECOG, NCCTG and SWOG, comparing adjuvant therapy with paclitaxel (P) to no further chemotherapy following four courses of doxorubicin (A) and cyclophospha-mide (C) | 600 mg/m2 of C + A at doses of either
every 3 weeks for four courses and either
Patients (pts) whose tumors were +ve were to receive subsequent tamoxifen (20 mg daily for 5 years); patients who received segmental mastectomies prior to study were to receive breast irradiation after recovery from treatment-related toxicities. | 3170 | Node-positive breast carcinoma following either mastectomy or segmental mastectomy and nodal dissections. | Median follow-up was 30.1 months. Of 2066 pts who were hormone receptor positive, 93% received tamoxifen. Based on a multivariate Cox model for disease-free survival, pts on AC+P had 22% risk reduction of disease recurrence compared to pts on AC (Hazard Ratio [HR]=0.78, 95% CI 0.67-0.91, p=0.0022) and 26% reduction in the risk of death (HR=0.74, 95% CI 0.60-0.92, p=0.0065). Increasing the dose of A higher than 60 mg/m2 had no effect on either disease-free survival or overall survival. Subset analysis including number of positive lymph nodes, tumor size, hormone receptor status, and menopausal status showed a reduction in hazard similar to above for disease-free and overall survival in all larger subsets with one exception; pts with receptor-positive tumors had a smaller reduction in hazard (HR=0.92) for disease-free survival with P than other groups. |
Breast Carcinoma (continued)
| Study Design | Treatments / Doses | No. of Pts. | Population | Endpoints/Conclusion |
After Failure of Initial Chemotherapy: Phase III multicenter, randomized trial comparing two dosage regimens of paclitaxel (P). |
| 471 | Patients (pts) who failed chemotherapy either in the adjuvant (30%) or metastatic (39%) setting or both (31%). At study entry, 60% had symptomatic disease with impaired performance status and 73% had visceral metastases. | The overall response rate was 26% (95% CI: 22 to 30%), with 17 complete and 99 partial responses. The median duration of response, measured from the first day of treatment, was 8.1 months (range: 3.4-18.1 + months). Overall, the median time to progression was 3.5 months (range: 0.03-17.1 months). Median survival was 11.7 months (range: 0-18.9 months). |
Adjuvant Breast Carcinoma Study: The adverse event profile for patients receiving paclitaxel subsequent to AC was consistent with that seen in previous clinical studies (see ADVERSE REACTIONS).
After Failure of Initial Chemotherapy: In addition to the Phase III trial described above, data from three Phase II clinical studies were used in support of the use of paclitaxel in patients with metastatic breast carcinoma. The adverse event profile for patients receiving paclitaxel subsequent to AC was consistent with that seen in previous clinical studies (see ADVERSE REACTIONS).
Non-Small Cell Lung Carcinoma (NSCLC)
| Study Design | Treatments / Doses | No. of Pts. | Population | Endpoints/Conclusion |
| Phase III multicenter, open label, randomized trial conducted by ECOG, comparing two dosage regimens of paclitaxel (P) in combination with cisplatin [c] to cisplatin [c] followed by etoposide (VP) |
| 599 | Non-Small Cell Lung Cancer | There were statistically significant differences favoring each of the P plus c arms for response rate and time to tumor progression. There was no statistically significant difference in survival between either P plus c arm and the c plus VP arm. In this study, the Functional Assessment of Cancer Therapy-Lung (FACT-L) questionnaire had seven subscales that measured subjective assessment of treatment. Of the seven, the Lung Cancer Specific Symptoms subscale favored P at 135 mg/m2 of P as a 24-hr infusion + 75 mg/m2 of c. For all other factors, there was no difference in the treatment groups. |
The adverse event profile for patients who received paclitaxel in combination with cisplatin was consistent with that seen in previous clinical studies (see ADVERSE REACTIONS).
DETAILED PHARMACOLOGY
In vitro
Paclitaxel exhibits cytotoxic activity against a wide variety of both human and rodent tumor cell lines in vitro including leukemia, non-small cell lung carcinoma, small cell lung carcinoma, colon carcinoma, CNS carcinoma, melanoma, renal carcinoma, ovarian carcinoma and breast carcinoma at IC50 concentration (defined as the concentration required to inhibit cell proliferation to 50% of that of untreated control cells) in the nM range. Paclitaxel blocks cell replication in the late G2 and/or M phases of the cell cycle. Additionally, paclitaxel produces unusual cytoskeletons characterized by discrete bundles or microtubules and the formation of abnormal spindle asters during mitosis. As a consequence of the disruption of the microtubule cytoskeleton, paclitaxel inhibits a variety of cell functions including chemotaxis, migration, cell spreading, polarization, generation of hydrogen peroxide and killing of phagocytosed microorganisms.
In addition to its ability to induce microtubule polymerization, exposure of murine macrophages to paclitaxel results in the release of tumor necrosis factor-a (TNF-a) accompanied by down regulation of the receptor.
In vivo
Paclitaxel has shown antitumor activity against many tumor models including leukemias and solid tumors and human solid xenografts. The table that follows summarizes paclitaxel’s activity.
| Tumor, Site | Form | Route | Activity |
| MURINE LEUKEMIAS | |||
L1210, ip P388,ip P1534,ip | * * * | ip ip ip | Borderline → modest Mild Mild → substantial |
| MURINE SOLID TUMORS | |||
ADJ/PC 6, ip C26, ip B16, ip M109, ip M109, ip (staged) M109, sc M109, src | * * * * ** ** ** | ip ip ip ip ip sc sc | Mild Mild Moderate → potentially curative Moderate → potentially curative Moderate → substantial Moderate Moderate |
| HUMAN TUMOR XENOGRAFTS | |||
CX-1, src LOX, ip MX-1, src A431, src A2780, src A2780, sc H2981, src HCT-116 L2987, src LX-1, src | * * * ** ** ** ** ** ** ** | sc ip sc iv iv iv iv iv iv iv | Mild → substantial Moderate → potentially curative Potentially curative Substantial Substantial Moderate Substantial Moderate Moderate Moderate |
* Suspension in hydroxypropylcellulose
** Paclitaxel , in ethanol/cremophor diluted with saline
TOXICOLOGY
ACUTE TOXICITY
| Species / Strain | No. / Sex / Group | Route | LD50 (mg/kg) |
| Rat/Sprague-Dawley | 5 M/F (RF)a 10 M/F (L)b | ip ip | 34 (combined) |
| Rat/Sprague-Dawley | 10 M/F | ip | M: 32 F: 36 |
| Rat/Sprague-Dawley | 5 M/F | iv | > 85 |
| Dog/Beagle | 1 M/F | iv | > 9 |
a Range-Finding phase
b Lethality phase
Signs of toxicity in rats were lethargy, rough coat, thinness, hunched posture, neck abscesses, soft stool, decreased body weight, squinted eyes, alopecia.
Signs of toxicity in dogs were decreased body weight.
SUBACUTE TOXICITY
| Species / Strain | No./ Group | Sex | Dose Rangea mg/kg/ day | Route | Duration | Drug Related Findings |
| Mouse/ CD2F1 | 5 5 | M F | 0, 1-15 | iv | 5 days | No drug related toxicities. |
| Mouse/ CD2F1 | 5 5 15 15 | M F M F | 0, 1-15* 0, 21-43** | ip ip | 5 days 5 days | 20 and 45 mg/kg/day : Decreased body weight > 10% 45 mg/kg/day: Rough coat, thin/hunched posture. All died. ≥ 24 mg/kg/day: Dose-related decreased body weight, rough coat, thin/hunched posture, ataxia, hypothermia, squinted eyes and dyspnea, deaths (74/88 M, 56/90 F). |
| Rat/ Sprague-Dawley | 5 5 10 10 | M F M F | 0, 5-45* 0, 5.3-14.2** | ip ip | 5 days 5 days | ≥ 8.66 mg/kg/day: Dose-related decreased body weight, rough coat, thin/hunched posture, stool changes, soiling, hypothermia, eye tearing and squinting, abscesses, deaths [(19/20 M 18/20 F)*; (44/70 M at all doses, 26/40 F)**]. |
SUBACUTE TOXICITY (continued)
| Species / Strain | No./ Group | Sex | Dose Rangea mg/kg/ day | Route | Duration | Drug Related Findings |
| Mouse/ CD2F1 | 1.0e+19 | M F M F M F M F M F | Negativeb Control Vehicle Control ½ LD10 10.79 13.05 LD10 21.57 26.09 LD50 25.50 29.52 | ip | 5 days | ½ LD10,LD10 and LD50 dose groups: Necrosis of developing spermatocytes. Giant cell formation. LD10 and LD50 dose groups: Decrease in reticulocyte and neutrophil values. Lower liver and testicular weights. Moderate to severe thymic cortical lymphoid depletion. Necrosis or atrophy of small intestinal mucosa and crypt cell hypoplasia. Neurophilic hyperplasia, eosinopenia, lymphoid hypoplasia and atypical megakaryocytes, deaths (2/10 M, 8/10 F at LD10; 8/10 M, 9/9 F at LD50). All dose groups: Dose-related decreased body weight, lethargy, rapid respiration, rough coat, thin/hunched posture, hypothermia, squinted eyes with exudate. |
SUBACUTE TOXICITY (continued)
| Species / Strain | No./ Group | Sex | Dose Rangea mg/kg/ day | Route | Duration | Drug Related Findings |
| Rat/ Sprague-Dawley | 1.0e+19 | M F M F M F M F M F | Negativeb Control Vehicle Control ½ LD10 2.55 4.29 LD10 5.11 8.58 LD50 7.47 9.99 | ip | 5 days | LD50 dose group: Testicular necrosis, visceral peritoneum inflammation (F only), deaths (3/10 M, 3/10 F). LD10 and LD50 dose-groups: Markedly decreased leukocyte and platelet counts. Weight loss, bone marrow hypoplasia, deaths (1/10 M, 3/10 F at LD10). All dose groups: Dose related thymic and splenic lymphoid depletion, rough coat, thin/hunched posture, lethargy, soft stool, neck abscesses. Decreased reticulocycte counts, white foci in submandibular lymph nodes and/or salivary glands. |
| Dog/ Beagle | 11 | M F | 0, 0.375, 0.75, 1.5, 3.0, 6.0 | iv | 5 days | All doses: Decreased body weight. Increased ALT, cholesterol, triglycerides and total lipids. Intestinal hemorrhage or agonal changes. Lymphoid depletion of tonsils and/or bronchial lymph node. ≥1.5 mg/kg/day: Marked decreases in leukocyte, reticulocyte, platelet, and erythrocyte counts. ≤1.5 mg/kg/day: Moderate to severe bone marrow hematopoietic hypoplasia. 3.0 to 6.0 mg/kg/day: Deaths (All) |
* Range Finding phase
**Lethality phase
a Paclitaxel in Cremaphor EL (50%): ethanol (50%) and then diluted with saline to provide dosing solutions b Untreated
CHRONIC TOXICITY
| Species / Strain | No./ Group | Sex | Dose Rangea mg/kg/day | Route | Duration | Drug Related Findings |
| Rat/ Sprague-Dawley | 1.01e+11 | M F M F M F | Neg. Cont., saline Vehicle Control 1, 3.3, 10 | iv | 1 month | 3.3 mg/kg/day: Slight decreases in erythrocyte, neutrophil and platelet counts and hemoglobin and hematocrit values; moderate decreases in leukocyte counts. Increased splenic extramedullary hematopoiesis and bone marrow hypoplasia. Moderate to severe decrease in reticulocyte counts. Minimal increase in lymphocyte counts. 10 mg/kg/day: Rough coat, alopecia, decreased body weight/weight gain and food and water intakes. Slight decreases in erythrocyte and neutrophil counts, hemoglobin and hemocrit values; moderate to severe decreases in reticulocyte count and slight increases in platelet and relative lymphocyte counts. Decreased weight of thymus, testes and seminal vesicles. Lower weights of testes and epididymides present at end of observation period. Microscopically, increased splenic extra medullary hematopoiesis and lymphoid depletion, thymic atrophy and lymphoid depletion, mandibular lymph node atrophy of lymph follicle, and lymphadenitis; bone marrow hypoplasia; hypospermatogenesis and atrophy of seminiferous tubules; glandular atrophy in seminal vesicle and prostate and giant cell formation in the epididymides. |
CHRONIC TOXICITY (continued)
| Species / Strain | No./ Group | Sex | Dose Rangea mg/kg/day | Route | Duration | Drug Related Findings |
| Dog/ Beagle | 5 5 3 3 3 3 5 5 | M F M F M F M F | Neg. Cont., saline Vehicle Control 0.3, 1 3 | iv | 1 month | 0.3 and 1 mg/kg/day: Reversible minimal decreases in bone marrow saline cellularity. 3 mg/kg/day: Interdigital cysts, swollen infusion sites, and transient decreased weight gain and food intake. Decreased erythrocyte numbers, hemoglobin concentration and hemocrit (M/F) and decreased leucocyte (severe neutropenia) counts in individual females. Lymphoid depletion of spleen or lymph nodes, duodenal inflammation and crypt dilation, decreased bone marrow cellularity, skin lesions and giant cell formation in the testes and epididymides. Residual drug-effects present in some lymphoid organs, duodenum, testes and skin at the end of recovery period. |
* Paclitaxel in Cremophor EL: ethanol (50/50) diluted with saline for dosing solutions
REPRODUCTION AND TERATOLOGY
| Species/ Strain | No./ Group | Sex | Route | Dose* and Frequency | Drug Related Findings |
SEGMENT I Rat/ Sprague-Dawley | 20 20 20 | M F F | iv | 0 (vehicle), 0 (saline) 0.1, 0.3, 1.0 mg/kg M:63 days prior to mating and during mating F: During mating and through day 7 of gestation 0 (Non-treated) | Body weight gain and food intake were lower in F0 males and females Days 25-63 and Days 28-62, respectively, of premating period. Body weight gain and food intake were lower in F0 females during Days 2-20 of gestation at the high dose level. Fertility indices in the F0 generation were lower at 1mg/kg/day compared to saline and vehicle control groups. Copulation indices were similar to control. Adrenal, uterine and ovarian weights lower in F0 dams compared to controls. Numbers of corpora lutea, implantations and live fetuses were decreased, and numbers of empty implantation sites and fetal deaths were increased 1 mg/kg/day. The no-effect dose was 0.3 mg/kg/day in both F0 and F1 generations. |
REPRODUCTION AND TERATOLOGY (continued)
| Species/ Strain | No./ Group | Sex | Route | Dose* and Frequency | Drug Related Findings |
SEGMENT II Rabbit/New Zealand White | 20 | F | iv | 0 (saline), 0 (vehicle), 0.3, 1, 3 mg/kg, Days 6-18 of presumed gestation. | Twelve of 20 does given the high dose died or were sacrificed as moribund. Clinical signs of toxicity in the does that died included red excreta, stool consistency changes, decreased activity, food intake decreases and body weight loss. Liver and kidney weights were increased and ovary weights were decreased in the does given the high dose. Litter group mean values for corpora lutea, litter size, live fetuses and the number of does with viable fetuses in the high dose group were reduced. Litter group mean values for resorption (total or early), percentage of dead or resorbed conceptuses and the number of does with all conceptuses dead or resorbed were increased in the high dose group. In summary, paclitaxel at 3 mg/kg/day caused severe maternal toxicity (mortality, abortions, clinical signs and reduced organ weights, body weights and food consumption) and severe developmental toxicity (reduced corpora lutea, litter size and live fetuses and increased resorption). Paclitaxel doses as high as 1mg/kg/day did not cause any maternal or fetal toxicity. |
* Paclitaxel in Cremophor EL: ethanol (50/50) diluted with saline for dosing solutions
MUTAGENECITY AND GENOTOXICITY
Paclitaxel was not mutagenic in the Ames/Salmonella and Escherichia Coli WP2 reverse mutation assays but was found to be clastogenic, in the in vitro cytogenetics assay in primary human lymphocytes.
Paclitaxel was genotoxic in vivo on the mouse erythropoietic system in the mouse bone marrow erythrocyte micronucleus assay.
REFERENCES
- 1. Berg S.L., Cowan K.H., Balis F.M., et al. Pharmacokinetics of Taxol and doxorubicin administered alone and in combination by continuous 72-hour infusion. J Nat Can Inst 1994; 86:143-145.
- 2. Brown T., Havlin K., Weiss G., Cagnola J., Kuhn J., Rizzo J., Craig J., Phillips J., and Van Hoff D. A phase I trial of taxol given by a 6-hour intravenous infusion. J Clin Oncol 1991; 9: 1261-1267.
- 3. Cabral F.R., Wible L., Brenner S., and Brinkley B.R. Taxol-requiring mutant of Chinese hamster ovary cells with impaired mitotic spindle assembly. J Cell Biol 1983; 97: 30-39.
- 4. Capri G., Munzone E., Tarenzi E., et al. Optic nerve disturbances: A new form of paclitaxel neurotoxicity. J Nat Cancer Inst. 1994; 86: 1099-1101.
- 5. DeBrabander M. A model for the microtubule organizing activity of the centrosomes and kinetochores in mammalian cells. Cell Biol Int Rep 1982; 6: 901-915.
- 6. Donehower R.C., Rowinsky E.K., Grochow L.B., et al. Phase I trial of taxol in patients with advanced cancer. Cancer Treat Reports 1987; 71(12): 1171-1177.
- 7. Dorr R.T., Snead K., Liddil, J.D. Skin Ulceration Potential of Paclitaxel in a Mouse Skin Model In Vivo. Cancer 1996; 78(l): 152-156.
- 8. Einzig A.I., Wiernik P.H., and Schwartz E.L. Taxol: A new agent active in melanoma and ovarian cancer. In New Drugs, Concepts and Results in Cancer Chemotherapy, FM Muggia (ed.), pp. 89-100. Kluwer Academic Publishers, Inc. (1992).
- 9. Georgakopoulos CD, Makri OE, Vasilakis P, Exarchou A. Angiographically silent cystoid macular edema secondary to paclitaxel therapy. Clin Exp Optom 2012; 95: 233-6.
- 10. Gianni L., Kearns C.M., Giani A., et al. Nonlinear pharmacokinetics and metabolism of paclitaxel and its pharmacokinetic/pharmacodynamic relationships in humans. J Clin Oncol 1995; 13: 180-190.
- 11. Grem T.L., Tutsch K.D., Simon K.J., Alberti D.B., Willson J.K.V., Tormey D.C., Swaminathan S., Trump D.L. Phase I study of taxol administered as a short iv infusion daily for 5 days. Cancer Treat Reports 1987; 71(12): 1179-1184.
- 12. Ham D.S., Lee J.E., Kim H.W., Yun I.H. A case of cystoid macular edema associated with paclitaxel chemotherapy. Korean J Ophthalmol 2012; 26: 388-90.
- 13. Harris J.W., Rahman A., Kim B.-R., et al. Metabolism of TAXOL by human hepatic microsomes and liver slices: Participation of cytochrome P450 3A4 and an unknown P450 enzyme. Cancer Res 1994; 54: 4026-4035.
- 14. Joshi M.M., Garretson B.R. Paclitaxel maculopathy. Arch Ophthalmol 2007; 125: 709-10.
- 15. Kecker R.W., Jamis-Dow C.A., Egorin M.J., et al. Effect of cimetidine, probenecid, and ketoconazole on the distribution, biliary secretion, and metabolism of [3H] TAXOL in the Sprague-Dawley rat. Drug Metab Disposit 1994; 22; 254-258.
- 16. Kelly K., Crowley J., Bunn P.A., et al. A Randomized Phase III Trial of Paclitaxel Plus Carboplatin (PC) Versus Vinorelbine Plus Cisplatin (VC) in Untreated Advanced Non-Small Cell Lung Cancer (NSCLC): A Southwest Oncology Group (SWOG) Trial.
- 17. Kuznetcova T.I., Cech P., Herbort C.P. The mystery of angiographically silent macular oedema due to taxanes. Int Ophthalmol 2012; 32: 299-304.
- 18. Legha S.S., Tenney D.M., Krakoff I.R. Phase I study of taxol using a 5-day intermittent schedule. J Clin Oncol 1986; 4(5): 762-766.
- 19. Manfredi J.J. and Horwitz S.B. An antimitotic agent with a new mechanism of action. Pharmacol Ther 1984; 25: 83-125.
- 20. Manfredi J.J., Parness J., and Horwitz S.B. Taxol binds to cellular microtubules. J Cell Biol 1982; 94: 688-696.
- 21. McGuire W.P., Rowinsky E.K., Rosenshein N.B., Grumbine F.C., Ettinger D.S., Armstrong D.K., and Donehower R.C. Taxol: A unique antineoplastic agent with significant activity in advanced ovarian epithelial neoplasms. Ann Int Med 1989; 111: 273-279.
- 22. McGuire W.P., Hoskins W.J., Brady M.F., Kugera P.R., Partridge E.E., Look K.Y., Clarke-Pearson D.L. and Davidson M. Cyclophosphamide and cisplatin compared with paclitaxel and cisplatin in patients with stage III and stage IV ovarian cancer. New Eng J Med 1996; 334: 1-6.
- 23. Mole-Bajer J. and Bajer A.S. Action of taxol on mitosis: modification of microtubule arrangements and function of the mitotic spindle in Haemanthus endosperm. J Cell Biol 1983; 96: 527-540.
- 24. Norton L., Slamon D., Leyland-Jones B., et al. Overall Survival (OS) Advantage to Simultaneous Chemotherapy (Crx) Plus the Humanized Anti-HER2 Monoclonal Antibody Herceptin (H) in HER2-Overexpressing (HER2+) Metastatic Breast Cancer (MBC).
- 25. O’Shaghnessy J.A., Fisherman J.S., Cowan K.H. Combination paclitaxel (TAXOL) and doxorubicin therapy for metastatic breast cancer. Sem Oncol 1994; 21(suppl 8): 19-23
- 26. Roberts L.P., Nath J., Friedman M.M. and Gallin J.I. Effects of taxol on human neutrophils. J Immunol 1982; 129: 2134-2141.
- 27. Rowinsky E.K., Burke P.J., Karp J.E., Tucker R.W. Ettinger D.S., and Donehower R.C. Phase I and pharmacodynamic study of taxol in refractory acute leukemias. Cancer Res 1989 49: 4640-4647.
- 28. Rowinsky E.K., Cazenave L.A., and Donehower R.C. Taxol: a novel investigational antimicrotubule agent. J Natl Canc Inst 1990; 82: 1247-1259.
- 29. Rowinsky E.K., Gilbert M.R., McGuire W.P., Noe D.A., Grochow L.B., Forastiere A.A., Erringer D.S., Lubejko B.G. Clark B., Sartorius S.E., Cornblath D.R., Hendricks C.B. and Donehower R.C. Sequences of taxol and cisplatin: A Phase I and pharmacologic study. J Clin Oncol 1991; 9(9): 1692-1703.
- 30. Sarosy G., Kohn E., Stone D.A., Rothenberg M., Jacob J., Adamo D.O., Ognibene F.P., Cunnoin R.E. and Reed E. Phase I study of taxol and granulocyte colony-stimulating factor in patients with refractory ovarian cancer. J Clin Oncol 1992; 10(7): 1165-1170.
- 31. Schiff P.B. and Horwitz S.B. Taxol stabilizes microtubules in mouse fibroblast cells. Proc Natl Acad Sci, USA 1980; 77: 1561-1565.
- 32. Seidman A.D., Barrett S., Canezo S. Photopsia during 3-hour paclitaxel administration at doses > or =250 mg/m2. J Clin Oncol 1994; 12:1741-1742.
- 33. Slichenmyer W.J., and Von Hoff D.D. Taxol: A new and effective anti-cancer drug. Anti-Cancer Drugs 1991; 2: 519-530.
- 34. Turner P.F. and Margolis R.L. Taxol-induced bundling of brain-derived microtubules. J Cell Biol 1984; 99: 940-946.
- 35. Venook A.P., Egorin M., Brown T.D., et al Paclitaxel (Taxol) in patients with liver dysfunction (CALGB 9264) pROC asco 1994; 13: 139 (Abstract #350).
- 36. Walsky RL, Obach RS, Gaman EA, et al. Selective Inhibition of Human Cytochrome P4502C8 by Montelukast. Drug Metabolism and Disposition 2005; 33 (3): 413-418.
- 37. Walsky RL, Gaman EA and Obach RS. Examination of 209 drugs for inhibition of cytochrome P450 2C8. J Clin Pharmacol 2005; 45: 68-78.
- 38. Waugh W.N., Trissel L.A., and Stella V.J. Stability, compatibility and plasticizer extraction of taxol injection diluted in infusion solutions and stored in various containers. Am J Hosp Pharm 1991; 48: 1520-1524.
- 39. Weiss R.B., Donehower R.C., Wiernik P.H. et al. Hypersensitivity reactions from taxol. J Clin Oncol 1990; 8: 1263-1268.
- 40. Wiernik P.H., Schwartz E.L., Strauman J.J., Dutcher J.P., Lipton R.B., and Einzig A. Phase I trial of taxol given as a 24-hour infusion every 21 days: Responses observed in metastatic melanoma. J Clin Oncol 1987; 5(8): 1232-1239.
- 41. Wiernik P.H., Schwartz E.L., Strauman J.J., Dutcher J.P., Lipton R.B., and Paietta E. Phase I clinical and pharmacokinetic study of taxol. Cancer Res 1987; 47: 2486-2493.
- 42. Wright M., Monsarrat B., Alvinerie P., et al. Hepatic metabolism and biliary excretion of taxol. Second National Cancer Institute Workshop on Taxol and Toxus. Alexandria, Virginia (1992).