


Product Monograph - Pro-Desvenlafaxine
INDICATIONS AND CLINICAL USE
Adults
PRO-DESVENLAFAXINE (desvenlafaxine succinate extended-release tablets) is indicated for the symptomatic relief of major depressive disorder.
The short-term efficacy of desvenlafaxine succinate has been demonstrated in placebo-controlled trials of up to 8 weeks.
The efficacy of desvenlafaxine succinate in maintaining an antidepressant response for up to 26 weeks, following response during 20 weeks of acute, open-label treatment, was demonstrated in a placebo-controlled trial.
Pediatrics (< 18 years of age)
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of desvenlafaxine succinate in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use.
Two placebo controlled studies in 587 pediatric patients 7 to 17 years of age with MDD failed to demonstrate efficacy; neither short term, placebo-controlled study demonstrated statistically or clinically significant differences between desvenlafaxine succinate and placebo (see WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm; also Special Populations, Pediatrics; ADVERSE REACTIONS, Pediatrics ACTION AND CLINICAL PHARMACOLOGY, Pediatrics).
CONTRAINDICATIONS
- PRO-DESVENLAFAXINE must not be used concomitantly in patients taking monoamine oxidase inhibitors (MAOIs), including linezolid, an antibiotic, methylene blue, a dye used in certain surgeries, or in patients who have taken MAOIs within the preceding 14 days due to the risk of serious, sometimes fatal, drug interactions with selective serotonin reuptake inhibitor (SSRI) or serotonin norepinephrine reuptake inhibitor (SNRI) treatment or with other serotonergic drugs. These interactions have been associated with symptoms that include tremor, myoclonus, diaphoresis, nausea, vomiting, flushing, dizziness, hyperthermia with features resembling neuroleptic malignant syndrome, seizures, rigidity, autonomic instability with possible rapid fluctuations of vital signs, and mental status changes that include extreme agitation progressing to delirium and coma. Based on the half-life of desvenlafaxine succinate, at least 7 days should be allowed after stopping desvenlafaxine succinate and before starting an MAOI.
- Hypersensitivity to desvenlafaxine succinate extended-release, venlafaxine hydrochloride or to any excipients in the desvenlafaxine formulation (see DOSAGE FORMS, COMPOSITION AND PACKAGING).
WARNINGS AND PRECAUTIONS
POTENTIAL ASSOCIATION WITH BEHAVIOURAL AND EMOTIONAL CHANGES, INCLUDING SELF-HARM.
Pediatrics: Placebo-Controlled Clinical Trial Data
Recent analyses of placebo-controlled clinical trial safety databases from Selective Serotonin Reuptake Inhibitors (SSRIs) and other newer anti-depressants suggest that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo.
The small denominators in the clinical trial database, as well as the variability in placebo rates, preclude reliable conclusions on the relative safety profiles among the drugs in the class.
PRO-DESVENLAFAXINE is not indicated for use in pediatric patients (see INDICATIONS).
Adults and Pediatrics: Additional data
There are clinical trial and post-marketing reports with SSRIs and other newer antidepressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm or harm to others. The agitation-type events include: akathisia, agitation, disinhibition, emotional lability, hostility, aggression, and depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages especially when initiating therapy or during any change in dose or dosage regimen. This includes monitoring for agitation-type emotional and behavioural changes.
An FDA meta-analysis of placebo-controlled clinical trials of antidepressant drugs in adult patients ages 18 to 24 years with psychiatric disorders showed an increased risk of suicidal behaviour with antidepressants compared to placebo.
Aggression
Aggression may occur in some patients who have received antidepressants, including desvenlafaxine treatment, dose reduction, or discontinuation. As with other antidepressants, desvenlafaxine should be used cautiously in patients with a history of aggression.
Discontinuation
Discontinuation effects are well known to occur with antidepressants, and sometimes these effects can be protracted and severe (see ADVERSE REACTIONS). Suicide/suicidal thoughts and aggression have been observed in patients during changes in desvenlafaxine dosing regimen, including during discontinuation (see WARNINGS AND PRECAUTIONS, Discontinuation Effects). It is therefore recommended that the dosage of desvenlafaxine be tapered gradually and individually and the patients be closely monitored during discontinuation (see DOSAGE AND ADMINISTRATION). In some patients, discontinuation could take months or longer.
Sexual Dysfunction
Serotonin-norepinephrine reuptake inhibitors (SNRIs) may cause symptoms of sexual dysfunction (see ADVERSE REACTIONS). There have been reports of long-lasting sexual dysfunction where the symptoms have continued despite discontinuation of SNRIs.
General
Concomitant Use of PRO-DESVENLAFAXINE with VENLAFAXINE
Since desvenlafaxine is the major active metabolite of venlafaxine, concomitant use of PRO-DESVENLAFAXINE with products containing Venlafaxine is not recommended since the combination of the two will lead to additive desvenlafaxine exposure.
Allergic Reactions
Patients should be advised to notify their physician if they develop a rash, hives or a related allergic phenomenon.
Bone Fracture Risk
Epidemiological studies show an increased risk of bone fractures following exposure to some antidepressants, including SSRIs/SNRIs. The risks appear to be greater at the initial stages of treatment, but significant increased risks were also observed at later stages of treatment. The possibility of fracture should be considered in the care of patients treated with PRO-DESVENLAFAXINE. Elderly patients and patients with important risk factors for bone fractures should be advised of possible adverse events which increase the risk of falls, such as dizziness and orthostatic hypotension, especially at the early stages of treatment but also soon after withdrawal. Preliminary data from observational studies show association of SSRIs/SNRIs and low bone mineral density in older men and women. Until further information becomes available, a possible effect on bone mineral density with long term treatment with SSRIs/SNRIs, including PRO-DESVENLAFAXINE, cannot be excluded, and may be a potential concern for patients with osteoporosis or major risk factors for bone fractures.
Carcinogenesis and Mutagenesis
For animal data see TOXICOLOGY.
Cardiovascular/Cerebrovascular
Caution is advised in administering PRO-DESVENLAFAXINE to patients with cardiovascular, cerebrovascular, or lipid metabolism disorders (see Clinical Trial Adverse Drug Reactions). Increases in blood pressure and heart rate were observed in clinical trials with desvenlafaxine succinate. Desvenlafaxine succinate has not been evaluated systematically in patients with a recent history of myocardial infarction, unstable heart disease, uncontrolled hypertension, or cerebrovascular disease. Patients with these diagnoses, except for cerebrovascular disease, were excluded from clinical trials.
Effects on blood pressure
Cases of elevated blood pressure requiring immediate treatment have been reported with desvenlafaxine in postmarketing experience, including reports of hypertensive crisis and malignant hypertension. Increases in blood pressure were observed in some patients in clinical trials, particularly with higher doses. Caution should be exercised in treating patients with underlying conditions that might be compromised by increases in blood pressure (see ADVERSE REACTIONS, Vital Sign Changes). Pre-existing hypertension should be controlled before treatment with PRO-DESVENLAFAXINE. Patients receiving PRO-DESVENLAFAXINE should have regular monitoring of blood pressure. Sustained blood pressure increases could have adverse consequences. For patients who experience a sustained increase in blood pressure while receiving PRO-DESVENLAFAXINE, either dose reduction or discontinuation should be considered.
Treatment with desvenlafaxine succinate at all doses from 50 mg/day to 400 mg/day in controlled studies was associated with sustained hypertension (defined as treatment-emergent supine diastolic blood pressure ≥ 90 mm Hg and ≥10 mm Hg above baseline for 3 consecutive visits). Table 1 provides the incidence of patients meeting criteria for sustained hypertension.
Table 1: Incidence (%) of Patients with Sustained Hypertension for All Short-Term Fixed- Dose Clinical Trials
| ---------- Desvenlafaxine succinate ----------------- | |||||
| Placebo | 50 mg | 100 mg | 200 mg | 400 mg | |
| Sustained hypertension | 0.5 | 1.3 | 0.7 | 1.1 | 2.3 |
Dependence/Tolerance
Although desvenlafaxine succinate has not been systematically studied in preclinical or clinical trials for its potential for abuse, no indication of drug-seeking behavior was seen in the clinical trials.
Discontinuation Symptoms
At the time that a medical decision is made to discontinue PRO-DESVENLAFAXINE, a gradual reduction in the dose, rather than an abrupt cessation, is recommended.
During marketing of SNRIs, and SSRIs, there have been post-marketing reports of adverse events occurring upon discontinuation of these drugs, particularly when abrupt, including the following: dysphoric mood, irritability, agitation, dizziness, sensory disturbances (e.g., paraesthesias, such as electric shock sensations), anxiety, confusion, headache, lethargy, emotional lability, insomnia, hypomania, tinnitus, seizures, visual impairment and hypertension. While these events are generally self-limiting, there have been reports of serious discontinuation symptoms. In addition, suicide/suicidal thoughts and aggression have been observed in patients during changes in desvenlafaxine dosing regimen, including during discontinuation.
Patients should be monitored for these symptoms when discontinuing treatment with PRO-DESVENLAFAXINE. A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, then resuming the previously prescribed dose may be considered. Subsequently, the physician may continue decreasing the dose but at a more gradual rate (see ADVERSE REACTIONS, Discontinuation Symptoms, and DOSAGE AND ADMINISTRATION, Discontinuing PRO-DESVENLAFAXINE). In some patients, discontinuation may need to occur over periods of months or longer.
Endocrine and Metabolism
Serum Cholesterol Elevation
Increases in cholesterol (total and LDL) and triglycerides were observed in some patients treated with desvenlafaxine succinate in placebo-controlled pre-marketing clinical trials, particularly with higher doses. Measurement of serum lipid levels should be considered during treatment.
Hyponatremia
Cases of hyponatremia and/or the Syndrome of Inappropriate Antidiuretic Hormone (SIADH) secretion have been described with SNRIs and SSRIs, usually in volume-depleted or dehydrated patients, including elderly patients and patients taking diuretics.
Gastrointestinal
Potential for Gastrointestinal Obstruction
Because the PRO-DESVENLAFAXINE do not appreciably change in shape in the gastrointestinal tract, PRO-DESVENLAFAXINE should not be administered to patients with pre-existing gastrointestinal narrowing (pathologic or iatrogenic, such as small bowel inflammatory disease, “short gut” syndrome due to adhesions or decreased transit time, past history of peritonitis, cystic fibrosis, chronic intestinal pseudo-obstruction, or Meckel’s diverticulum).
There have been rare reports of obstructive symptoms in patients with known strictures in association with the ingestion of other drugs in nondeformable controlled-release formulations, and very rare reports of obstructive symptoms associated with the use of nondeformable controlled-release formulations in patients without known gastrointestinal stricture. Due to the controlled-release design, PRO-DESVENLAFAXINE should only be used in patients who are able to swallow the tablets whole. (See DOSAGE AND ADMINISTRATION; Recommended Dose and Dosage Adjustment).
Hematologic
Abnormal Bleeding
SSRIs and SNRIs, including PRO-DESVENLAFAXINE, may increase the risk of bleeding events by causing abnormal platelet aggregation. Concomitant use of acetylsalicylic acid (ASA), nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin and other anticoagulants may add to the risk. Case reports and epidemiological studies (case-control and cohort design) have demonstrated an association between use of drugs that interfere with serotonin reuptake and the occurrence of gastrointestinal bleeding. Bleeding events related to SSRIs and SNRIs use have ranged from ecchymoses, hematomas, epistaxis, and petechiae to life-threatening hemorrhages.
Patients should be cautioned about the risk of bleeding associated with the concomitant use of PRO-DESVENLAFAXINE and NSAIDs, ASA, or other drugs that affect coagulation (see DRUG INTERACTIONS, Drugs Affecting Platelet Function). Caution is advised in patients with a history of bleeding disorder or predisposing conditions (e.g, thrombocytopenia).
Interstitial Lung Disease and Eosinophilic Pneumonia
Interstitial lung disease and eosinophilic pneumonia associated with venlafaxine (the parent drug of desvenlafaxine succinate) therapy have been rarely reported. The possibility of these adverse events should be considered in patients treated with PRO-DESVENLAFAXINE who present with progressive dyspnea, cough, or chest discomfort. Such patients should undergo a prompt medical evaluation, and discontinuation of PRO-DESVENLAFAXINE should be considered.
Neurologic
Seizures
Cases of seizures have been reported in trials with desvenlafaxine succinate. Desvenlafaxine succinate should be prescribed with caution in patients with a seizure disorder. Desvenlafaxine has not been systematically evaluated in patients with a seizure disorder.
Serotonin Syndrome or Neuroleptic Malignant Syndrome (NMS)-Like Reactions
As with other serotonergic agents, serotonin syndrome or Neuroleptic Malignant Syndrome (NMS)-like reactions, a potentially life-threatening condition, have been reported with SNRIs and SSRIs alone, including desvenlafaxine succinate treatment, particularly with concomitant use of other agents that may affect the serotonergic neurotransmitter systems (such as amphetamines, triptans, serotonin reuptake inhibitors, sibutramine, MAOIs (including linezolid, an antibiotic, and methylene blue), St. John’s Wort (Hypericum perforatum) and/or lithium) and with drugs that impair metabolism of serotonin or with antipsychotics or other dopamine antagonists. Serotonin syndrome symptoms may include mental status changes (e.g., agitation, hallucinations, and coma), autonomic instability (e.g., tachycardia, labile blood pressure, and hyperthermia), neuromuscular aberrations (e.g., hyperreflexia, incoordination) and/or gastrointestinal symptoms (e.g., nausea, vomiting, and diarrhea). Serotonin syndrome, in its most severe form, can resemble NMS, which includes hyperthermia, muscle rigidity, autonomic instability with possible rapid fluctuation of vital signs, and mental status changes.
If concomitant treatment with desvenlafaxine and other agents that may affect the serotonergic and/or dopaminergic neurotransmitter system (such as another SSRI/SNRI) or a 5- hydroxytryptamine receptor agonist (triptan) is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. The concomitant use of desvenlafaxine with serotonin precursors (such as tryptophan supplements) is not recommended (see DRUG INTERACTIONS, Serotonin Syndrome).
Treatment with PRO-DESVENLAFAXINE and any concomitant serotonergic or antidopaminergic agents, including antipsychotics, should be discontinued immediately if the above events occur and supportive symptomatic treatment should be initiated.
Ophthalmologic
Angle-Closure Glaucoma
As with other antidepressants, PRO-DESVENLAFAXINE can cause mydriasis, which may trigger an angle-closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Psychiatric
Mania/hypomania
Mania/hypomania may occur in a small proportion of patients with mood disorders who have received medication to treat depression, including desvenlafaxine succinate. During clinical studies, mania and hypomania were reported in approximately 0.15% (12/8,453) of patients treated with desvenlafaxine succinate. Activation of mania/hypomania has also been reported in a small proportion of patients with major affective disorder who were treated with other marketed antidepressants. As with all antidepressants, PRO-DESVENLAFAXINE should be used cautiously in patients with a history or family history of mania or hypomania.
A major depressive episode may be the initial presentation of bipolar disorder. Patients with bipolar disorder may be at an increased risk of experiencing manic episodes when treated with antidepressants alone. Therefore, the decision to initiate symptomatic treatment of depression should only be made after patients have been adequately assessed to determine if they are at risk for bipolar disorder.
Special Populations
Pregnant Women
The safety of desvenlafaxine in human pregnancy has not been established. Studies have demonstrated that desvenlafaxine crosses the human placenta. The extent of exposure to desvenlafaxine succinate in pregnancy during clinical trials was very limited. There are no adequate and well-controlled studies in pregnant women. Therefore, desvenlafaxine should be used during pregnancy only if the potential benefits justify the potential risks. If desvenlafaxine succinate is used until or shortly before birth, discontinuation effects in the newborn should be considered.
Post-marketing reports indicate that some neonates exposed to SNRIs, SSRIs, or other newer antidepressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyper-reflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SNRIs, SSRIs and other newer antidepressants, or, possibly a drug discontinuation syndrome. It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome (see DRUG INTERACTIONS). When treating a pregnant woman with PRO-DESVENLAFAXINE during the third trimester, the physician should carefully consider the potential risks and benefits of treatment.
Any change in antidepressant medication (including dosage) during pregnancy should be discussed with the attending physician beforehand to discuss the benefits/risks with the patient.
Exposure to SNRIs in mid to late pregnancy may increase the risk for preeclampsia, and exposure to SNRIs near delivery may increase the risk for postpartum hemorrhage.
Patients should be advised to notify their physician if they become pregnant or intend to become pregnant during therapy.
Labour and Delivery
The effect of desvenlafaxine on labour and delivery in humans is unknown. PRO-DESVENLAFAXINE should be used during labour and delivery only if the potential benefits justify the potential risks.
Nursing Women
Desvenlafaxine (O-desmethylvenlafaxine, a metabolite of desvenlafaxine) is excreted in human milk. The effects in infants have not been established. PRO-DESVENLAFAXINE should only be taken by breastfeeding women if the expected benefits outweigh any possible risk.
Pediatric
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of desvenlafaxine succinate in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
Two placebo controlled studies in 587 pediatric patients 7 to 17 years of age with MDD failed to demonstrate efficacy; neither short term, placebo-controlled study demonstrated statistically or clinically significant differences between desvenlafaxine succinate and placebo (see ACTION AND CLINICAL PHARMACOLOGY, Pediatrics).
The long-term safety, including effects on growth, maturation, and behavioural development, in patients under 18 years of age has not been systematically evaluated. (See ADVERSE REACTIONS, Adverse Drug Reactions in Pediatrics).
Geriatrics (≥ 65 years of age)
Of the 4,158 patients in clinical trials with desvenlafaxine succinate, 6% were 65 years of age or older. No overall differences in safety or efficacy were detected between these subjects and younger subjects. However, there was a higher incidence of increases in systolic blood pressure in patients ≥ 65 years of age compared to patients < 65 years of age treated with desvenlafaxine succinate. In addition, there was a higher incidence of systolic orthostatic hypotension in patients
≥ 65 years of age compared to all adults treated with desvenlafaxine. For elderly patients, possible reduced renal clearance of desvenlafaxine should be considered when determining dose (see Dosing Considerations, Geriatrics and ACTION AND CLINICAL PHARMACOLOGY, Geriatrics). Greater sensitivity of some older individuals cannot be ruled out.
Monitoring and Laboratory Tests
Serum Lipids
Increases in cholesterol (total and LDL) and triglycerides were observed in some patients treated with desvenlafaxine succinate in placebo-controlled pre-marketing clinical trials, particularly with higher doses. Measurement of serum lipid levels should be considered during treatment.
Heart Rate and Blood Pressure
Increases in heart rate and blood pressure were observed in some patients in clinical trials, particularly with higher doses. Measurement of blood pressure is recommended prior to initiating treatment and regularly during treatment with desvenlafaxine succinate (see ADVERSE REACTIONS, Vital Sign Changes).
Self-Harm
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages. Patients, their families, and their caregivers should be encouraged to be alert to the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, worsening of depression, and suicidal ideation, especially when initiating therapy or during any change in dose or dosage regimen. (See WARNINGS AND PRECAUTIONS, POTENTIAL ASSOCIATION WITH BEHAVIOURAL AND EMOTIONAL CHANGES, INCLUDING SELF-HARM).
ADVERSE REACTIONS
Adverse Drug Reaction Overview
The safety of desvenlafaxine succinate in major depressive disorder was evaluated in 8,453 patients exposed to at least one dose of desvenlafaxine succinate.
The most commonly observed treatment emergent adverse events (all-causality) (incidence of 5% or greater for the desvenlafaxine succinate pooled 50- to 400-mg doses, and incidence higher than placebo) in desvenlafaxine succinate treated MDD patients in clinical trials were: nausea, headache, dry mouth, dizziness, insomnia, hyperhidrosis, constipation, diarrhea, somnolence, fatigue, decreased appetite, vomiting, and blood pressure increased, and, in men, and erectile dysfunction.
Adverse Events Reported as Reasons for Discontinuation of Treatment in MDD Clinical Trials
In the 8-week placebo-controlled, pre-marketing trials for MDD, 12% of the 1,834 patients who received desvenlafaxine succinate (50-400 mg/day) discontinued treatment due to an adverse experience, compared with 3% of the 1,116 placebo-treated patients in those trials.
At the recommended dose of 50 mg, the discontinuation rate due to an adverse experience for desvenlafaxine succinate (4.1%) was similar to the rate for placebo (3.8%) and only 1% of patients discontinued due to nausea.
The most common adverse reactions leading to discontinuation (i.e., leading to discontinuation in at least 2% and incidence higher than placebo) of the desvenlafaxine succinate-treated patients in short-term trials of up to 8 weeks were: nausea (4%); dizziness, headache and vomiting (2% each).
Clinical Trial Adverse Drug Reactions
Because clinical trials are conducted under very specific conditions the adverse reaction rates observed in the clinical trials may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse drug reaction information from clinical trials is useful for identifying drug-related adverse events and for approximating rates.
Adverse Reactions in MDD Clinical Trials
Desvenlafaxine succinate was evaluated for safety in 8,453 patients diagnosed with major depressive disorder who participated in multiple-dose trials, representing 2,807 patient-years of exposure. Among these 8,453 desvenlafaxine succinate-treated patients, 2,495 patients participated in 8-week, placebo-controlled trials at doses ranging from 50 to 400 mg/day. Of the total 8,453 subjects exposed to at least 1 dose of desvenlafaxine succinate, 2,140 were exposed to desvenlafaxine succinate for greater than 6 months and 521 were exposed for 1 year.
Premarket Clinical Trials
Treatment-Emergent Adverse Events Occurring at an Incidence of ≥ 2% Among Desvenlafaxine Succinate-treated Patients in Short-Term Placebo-controlled Trials
Table 2 lists alphabetically by body system, the treatment-emergent adverse events that occurred with an incidence ≥2% and greater than placebo (pooled 8-week placebo-controlled, premarket clinical trials).
Reported treatment emergent adverse events were classified using a standard MedDRA-based Dictionary terminology.
Table 2: Treatment Emergent Adverse Events (≥2% in Any Desvenlafaxine Succinate Group and More Frequent than Placebo): Percentage of Subjects in Short-Term, Placebo-Controlled MDD Studies
| Percentage of Patients Reporting Reaction | |||||
System Organ Class Preferred Term | desvenlafaxine succinate | ||||
| Placebo (n=636) | 50 mg (n=317) | 100 mg (n=424) | 200 mg (n=307) | 400 mg (n=317) | |
| Cardiac disorders | |||||
| Palpitations | 2 | 1 | 3 | 2 | 3 |
| Tachycardia | 1 | 1 | <1 | 1 | 2 |
| Ear and labyrinth disorders | |||||
| Tinnitus | 1 | 2 | 1 | 1 | 2 |
| Vertigo | 1 | 2 | 1 | 5 | 3 |
| Eye disorders | |||||
| Eye pain | <1 | 1 | 2 | <1 | <1 |
| Mydriasis | <1 | 2 | 2 | 6 | 6 |
| Vision blurred | 1 | 3 | 4 | 4 | 4 |
| Gastrointestinal disorders | |||||
| Abdominal pain | 2 | 4 | 3 | 1 | 3 |
| Constipation | 4 | 9 | 9 | 10 | 14 |
| Diarrhea | 9 | 11 | 9 | 7 | 5 |
| Dry mouth | 9 | 11 | 17 | 21 | 25 |
| Dyspepsia | 4 | 2 | 3 | 3 | 5 |
| Flatulence | 1 | 2 | 2 | 2 | 2 |
| Nausea | 10 | 22 | 26 | 36 | 41 |
| Stomach discomfort | 1 | 2 | 1 | 1 | 1 |
| Vomiting | 3 | 3 | 4 | 6 | 9 |
| General disorders and administration site conditions | |||||
| Chest pain | 0 | 0 | 1 | 1 | 2 |
| Chills | 1 | 1 | <1 | 3 | 4 |
| Fatigue | 4 | 7 | 7 | 10 | 11 |
| Feeling jittery | 1 | 1 | 2 | 3 | 3 |
| Irritability | 1 | 2 | 2 | 2 | 2 |
| Infections and infestations | |||||
| Gastroenteritis viral | 1 | 0 | 1 | 2 | <1 |
| Influenza | 1 | 1 | 1 | 2 | 4 |
| Sinusitis | 1 | 2 | 1 | 2 | 2 |
| Urinary tract infection | <1 | 1 | 1 | 1 | 2 |
| Injury, poisoning and procedural complications | |||||
| Accidental overdose | 1 | 0 | 1 | 1 | 2 |
| Investigations | |||||
| Blood pressure increased | 1 | 1 | 1 | 2 | 2 |
| Weight decreased | 1 | 2 | 1 | 1 | 2 |
| Metabolism and nutrition disorders | |||||
Table 2: Treatment Emergent Adverse Events (≥2% in Any Desvenlafaxine Succinate Group and More Frequent than Placebo): Percentage of Subjects in Short-Term, Placebo-Controlled MDD Studies
| Percentage of Patients Reporting Reaction | |||||
System Organ Class Preferred Term | desvenlafaxine succinate | ||||
| Placebo (n=636) | 50 mg (n=317) | 100 mg (n=424) | 200 mg (n=307) | 400 mg (n=317) | |
| Decreased appetite | 2 | 5 | 8 | 10 | 10 |
| Increased appetite | 1 | 2 | 1 | 0 | 1 |
| Musculoskeletal and connective tissue disorders | |||||
| Muscle spasms | 1 | 2 | 3 | 2 | 2 |
| Muscle tightness | 1 | 1 | 2 | 1 | <1 |
| Nervous system disorders | |||||
| Disturbance in attention | <1 | <1 | 1 | 2 | 1 |
| Dizziness | 5 | 13 | 10 | 15 | 16 |
| Dysgeusia | 1 | 1 | 1 | 1 | 2 |
| Headache | 23 | 20 | 22 | 29 | 25 |
| Migraine | 1 | 1 | <1 | 1 | 2 |
| Paresthesia | 1 | 2 | 2 | 1 | 3 |
| Sedation | 1 | 2 | 4 | 3 | 4 |
| Somnolence | 4 | 4 | 9 | 12 | 12 |
| Tremor | 2 | 2 | 3 | 9 | 9 |
| Psychiatric disorders | |||||
| Abnormal dreams | 1 | 2 | 3 | 2 | 4 |
| Agitation | 1 | 0 | 1 | 1 | 3 |
| Anorgasmia | 0 | <1 | 2 | 2 | 6 |
| Anxiety | 2 | 3 | 5 | 4 | 4 |
| Initial insomnia | 1 | 2 | 2 | 0 | 2 |
| Insomnia | 6 | 9 | 12 | 14 | 15 |
| Libido decreased | 1 | 2 | 3 | 3 | 2 |
| Middle insomnia | 1 | 1 | 1 | 3 | 3 |
| Nervousness | 1 | <1 | 1 | 2 | 2 |
| Orgasm abnormal | <1 | 1 | 1 | 1 | 2 |
| Sleep disorder | <1 | 1 | <1 | 2 | 1 |
| Renal and urinary disorders | |||||
| Dysuria | <1 | <1 | 0 | 3 | 2 |
| Urinary hesitation | 0 | <1 | 1 | 2 | 2 |
| Reproductive system and breast disorder | |||||
| Dysmenorrhea | 1 | 0 | 1 | 2 | <1 |
| Ejaculation delayed | <1 | <1 | 2 | 3 | 3 |
| Ejaculation disorder | 0 | 0 | 1 | 1 | 2 |
| Erectile dysfunction | 1 | 1 | 2 | 3 | 5 |
| Respiratory, thoracic and mediastinal disorders | |||||
| Yawning | <1 | 1 | 1 | 4 | 3 |
Table 2: Treatment Emergent Adverse Events (≥2% in Any Desvenlafaxine Succinate Group and More Frequent than Placebo): Percentage of Subjects in Short-Term, Placebo-Controlled MDD Studies
| Percentage of Patients Reporting Reaction | |||||
System Organ Class Preferred Term | desvenlafaxine succinate | ||||
| Placebo (n=636) | 50 mg (n=317) | 100 mg (n=424) | 200 mg (n=307) | 400 mg (n=317) | |
| Skin and subcutaneous tissue disorders | |||||
| Hyperhidrosis | 4 | 10 | 11 | 18 | 21 |
| Night sweats | 1 | 2 | 1 | 1 | 1 |
| Rash | <1 | 1 | 1 | 2 | <1 |
| Vascular disorders | |||||
| Hot flush | <1 | 1 | 1 | 2 | 2 |
| Hypertension | 1 | 1 | 1 | 2 | 1 |
Sexual Dysfunction Treatment Emergent Adverse Events
Table 3 shows the incidence of sexual dysfunction treatment emergent adverse events that occurred in ≥1% desvenlafaxine succinate-treated MDD patients in any fixed dose group (8- week, placebo-controlled, fixed and flexible-dose, pre-marketing clinical trials).
Table 3: Sexual Dysfunction Treatment Emergent Adverse Events (≥ 1% in Men or Women in any Desvenlafaxine Succinate Group) During the On-Therapy Period: Percentage of Subjects in Short-Term, Placebo-Controlled MDD Studies
| Desvenlafaxine succinate | |||||||||||
Placebo (n=239) | 50 mg (n=108) | 100 mg (n=157) | 200 mg (n=131) | 400 mg (n=154) | |||||||
| Men only | |||||||||||
| Anorgasmia | 0 | 0 | 3 | 5 | 8 | ||||||
| Libido decreased | 1 | 4 | 5 | 6 | 3 | ||||||
| Orgasm abnormal | 0 | 0 | 1 | 2 | 3 | ||||||
| Ejaculation delayed | <1 | 1 | 5 | 7 | 6 | ||||||
| Erectile dysfunction | 1 | 3 | 6 | 8 | 11 | ||||||
| Ejaculation disorder | 0 | 0 | 1 | 2 | 5 | ||||||
| Ejaculation failure | 0 | 1 | 0 | 2 | 2 | ||||||
| Sexual dysfunction | 0 | 1 | 0 | 0 | 2 | ||||||
| Desvenlafaxine succinate | |||||||||||
Placebo (n=397) | 50 mg (n=209) | 100 mg (n=267) | 200 mg (n=176) | 400 mg (n=163) | |||||||
| Women only | |||||||||||
| Anorgasmia | 0 | 1 | 1 | 0 | 3 | ||||||
Other Treatment Emergent Adverse Events Observed During Pre-Market and Post-Market Clinical Trials
All MDD Clinical Trials
The following is a list of MedDRA preferred terms that reflect treatment-emergent adverse events that were reported by patients treated with desvenlafaxine succinate throughout the dose ranges studied (10 to 400 mg) during both short-term and long-term clinical trials. In general, the adverse events were most frequent in the first week of treatment.
Treatment Emergent Adverse Events are categorized by system organ class and listed in order of decreasing frequency using the following definitions:
Very common: ≥10% of patients Common: ≥1% and <10% of patients Uncommon: ≥0.1% and <1% of patients Rare: ≥0.01% and <0.1% of patients Very rare: <0.01% of patients
| System Organ Class | Treatment Emergent Adverse Events | |
| Immune System Disorders | ||
| Uncommon | Hypersensitivity | |
| Metabolism and Nutrition Disorders | ||
| Common | Decreased appetite | |
| Rare | Hyponatraemia | |
| Psychiatric Disorders | ||
| Very common | Insomnia | |
| Common | Withdrawal syndrome, anxiety, nervousness, abnormal dreams, irritability, libido decreased, anorgasmia | |
| Uncommon | Depersonalisation, orgasm abnormal | |
| Rare | Mania, hypomania, hallucination | |
| Nervous System Disorders | ||
| Very common | Headache, dizziness, somnolence | |
| Common | Tremor, paraesthesia, disturbance in attention, dysgeusia | |
| Uncommon | Syncope, dyskinesia | |
Rare Eye Disorders | Convulsion, dystonia | |
| Common | Vision blurred, mydriasis | |
| Ear and Labyrinth Disorders | ||
Common Cardiac Disorders | Vertigo, tinnitus | |
Common Vascular Disorders | Palpitations, tachycardia | |
| Common | Blood pressure increased, hot flush | |
| Uncommon | Orthostatic hypotension, peripheral coldness | |
| Respiratory, Thoracic and Mediastinal Disorders | ||
| System Organ Class | Treatment Emergent Adverse Events | |
| Common | Yawning | |
| Uncommon | Epistaxis | |
| Gastrointestinal Disorders | ||
| Very common | Nausea, dry mouth | |
| Common | Constipation, diarrhea, vomiting | |
| Skin and Subcutaneous Tissue Disorders | ||
| Very common | Hyperhidrosis | |
| Common | Rash | |
| Uncommon | Alopecia | |
| Rare | Angioedema, photosensitivity reaction | |
| Musculoskeletal and Connective Tissue and Bone Disorders | ||
| Common | Musculoskeletal stiffness | |
| Renal and Urinary Disorders | ||
| Uncommon | Urinary retention, urinary hesitation, proteinuria | |
| Reproductive System and Breast Disorders | ||
| Common | Erectile dysfunction, ejaculation delayed | |
| Uncommon | Ejaculation disorder, ejaculation failure, sexual dysfunction | |
| General Disorders and Administration Site Conditions | ||
| Common | Fatigue, asthenia, chills, feeling jittery | |
| Investigations | ||
| Common | Liver function test abnormal, weight increased, weight decreased | |
| Uncommon | Blood cholesterol increased, blood triglycerides increased, blood prolactin increased | |
ADR = adverse drug reaction; MDD = major depressive disorder.
Ischemic cardiac adverse events
In clinical trials, there were uncommon reports of ischemic cardiac adverse events, including myocardial ischemia, myocardial infarction, and coronary occlusion requiring revascularization; these patients had multiple underlying cardiac risk factors. More patients experienced these events during desvenlafaxine treatment as compared to placebo (see WARNINGS AND PRECAUTIONS/Cardiovascular/Cerebrovascular).
Discontinuation Symptoms
Adverse drug reactions reported in association with abrupt discontinuation, dose reduction or tapering of treatment in MDD pre-market clinical trials at a rate of ≥5% include: dizziness, nausea, headache, irritability, diarrhea, anxiety, abnormal dreams, fatigue, and hyperhidrosis. In general, discontinuation events occurred more frequently with longer duration of therapy (see DOSAGE AND ADMINISTRATION and WARNINGS AND PRECAUTIONS).
Orthostatic Hypotension
Of the 4,158 patients in pre-market clinical trials with desvenlafaxine succinate, 6% were 65 years of age or older. No overall differences in safety or efficacy were detected between these subjects and younger subjects. However, there was a higher incidence of orthostatic hypotension in patients ≥ 65 years of age compared to patients <65 years of age treated with desvenlafaxine.
Greater sensitivity of some older individuals cannot be ruled out. For elderly patients, possible reduced renal clearance of desvenlafaxine should be considered when determining dose (see DOSAGE AND ADMINISTRATION, Dosing Considerations, Geriatrics and ACTION AND CLINICAL PHARMACOLOGY, Geriatrics).
ECG Changes
Electrocardiograms were obtained from 1,492 desvenlafaxine succinate-treated patients with major depressive disorder and 984 placebo-treated patients in pre-market clinical trials lasting up to 8 weeks. No clinically relevant differences were observed between desvenlafaxine succinate- treated and placebo-treated patients for QT, QTc, PR, and QRS intervals. In a thorough QTc study with prospectively determined criteria, desvenlafaxine did not cause QT prolongation. No difference was observed between placebo and desvenlafaxine treatments for the QRS interval (see ACTION AND CLINICAL PHARMACOLOGY).
A thorough QTc study was designed to assess the potential effect of 200 and 600 mg of desvenlafaxine succinate on QT interval prolongation.
Table 4: Estimated and 90% Confidence Interval for QTc Changes from Time-Matched Baseline Relative to Placebo at Hour 8 after Dose with Different Heart Rate Correctionsa
| Treatment | Fridericia’s QT Correction (ms) | Population QT Correction (ms) | |||
| Desvenlafaxine succinate 200 mgb | 1.5 (-0.88, 3.88) | 3.18 (0.87, 5.50) | |||
| Desvenlafaxine succinate 600 mgb | -2.43 (-4.90, 0.04) | 0.98 (-1.42, 3.38) | |||
Moxifloxacin 400 mg (Active control) | 10.80 (8.44, 13.16) | 10.92 (8.62, 13.22) | |||
| |||||
Abnormal Hematologic and Clinical Chemistry Findings
Serum Lipids
Elevations in fasting serum total cholesterol, LDL cholesterol, and triglycerides occurred in the controlled trials. Some of these abnormalities were considered potentially clinically significant (see WARNINGS AND PRECAUTIONS, Serum Cholesterol Elevation and Monitoring and Laboratory Tests, Serum Lipids).
The percentage of subjects who exceeded a predetermined threshold for values of outliers is represented in Table 5.
Table 5: Proportion (%) of Subjects With Lipid Abnormalities of Potential Clinical Significance for All Short-Term, Placebo-Controlled Clinical Trials
| --------Desvenlafaxine succinate-------- | ||||||
| Placeboa | 50 mg | 100 mg | 200 mg | 400 mg | 50-400 mga | |
Total Cholesterol Increase ≥1.29 mmol/L and absolute value ≥6.75 mmol/L | 2 | 3 | 4 | 4 | 10 | 5 |
LDL Cholesterol Increase ≥1.29 mmol/L and absolute value ≥4.91 mmol/L | <1 | 1 | 0 | 1 | 2 | 1 |
Triglycerides ≥3.7 mmol/L | 3 | 2 | 1 | 4 | 6 | 3 |
| a. Includes data from all short-term, placebo-controlled studies including fixed-dose and flexible-dose studies. | ||||||
Proteinuria
In pre-market placebo-controlled studies 6.4% of subjects treated with desvenlafaxine succinate had treatment-emergent proteinuria. Proteinuria was usually of trace amounts and was not associated with increases in BUN or creatinine or adverse events. The mechanism of the enhanced protein excretion is not clear but may be related to noradrenergic stimulation.
Vital Sign Changes
Tables 6 and 7 summarize the changes that were observed in pre-market placebo-controlled, short-term, premarketing trials with desvenlafaxine succinate in patients with MDD.
Table 6: Mean Changes, Vital Signs, at Final On-Therapy for All Short-term, Fixed-dose Controlled Trials | |||||||||||
| -------Desvenlafaxine succinate---------- | |||||||||||
| Placebo | 50 mg | 100 mg | 200 mg | 400 mg | |||||||
| Blood Pressure | |||||||||||
| Supine systolic bp (mm Hg) | -1.4 | 1.2 | 2.0 | 2.5 | 2.1 | ||||||
| Supine diastolic bp (mm Hg) | -0.6 | 0.7 | 0.8 | 1.8 | 2.3 | ||||||
| Pulse rate | |||||||||||
| Supine pulse (bpm) | -0.3 | 1.3 | 1.3 | 0.9 | 4.1 | ||||||
| Weight (kg) | 0.0 | -0.4 | -0.6 | -0.9 | -1.1 | ||||||
At the final on-therapy assessment in the 6-month, double-blind, placebo-controlled phase of a long-term trial in patients who had responded to desvenlafaxine succinate during the initial 12- week, open-label phase, there was no statistical difference in mean weight change between desvenlafaxine succinate- and placebo-treated patients.
Table 7 provides the incidence of patients meeting criteria for sustained hypertension (defined as treatment-emergent supine diastolic blood pressure ≥ 90 mm Hg and ≥10 mm Hg above baseline for 3 consecutive visits).
Table 7: Incidence (%) of Patients with Sustained Hypertension for All Short-Term Fixed- Dose Clinical Trials
| -------Desvenlafaxine succinate----------- | |||||
| 50 mg | 100 mg | 200 mg | 400 mg | ||
| Placebo | |||||
| Sustained hypertension | 0.5 | 1.3 | 0.7 | 1.1 | 2.3 |
Adverse Drug Reactions in Pediatrics (<18 years of age)
The safety and efficacy of desvenlafaxine succinate in children under the age of 18 years have not been established, and it is not indicated for this population. (see WARNINGS AND PRECAUTIONS, Special Populations, Pediatrics).
All of the adverse events described above for adults with MDD should be considered in the case of children and adolescents taking PRO-DESVENLAFAXINE. Additional adverse events of note (including laboratory values and vitals) are summarized below.
The listed events are those identified as worse in children compared to adults at the recommended therapeutic dose, due to greater frequency rates and/or greater differential from placebo.
Table 8: Adverse Events during short-term (8 weeks) treatment of children and adolescents with Major Depressive Disorder that were identified as worse in pediatrics compared to adults, or unique to pediatrics and greater than placebo
| Age Group | Desvenlafaxine succinate | Placebo | |||||||||
| Frequency | n/N | Frequency | n/N | ||||||||
| Pooled (Ages 7-11 and 12-17) | |||||||||||
Weight loss1 (≥3.5% of baseline weight) | 17% | 60/356* | 7% | 16/231* | |||||||
| Upper abdominal pain 2 | 10% | 34/358 | 7% | 16/232 | |||||||
| Ages 7-11 | |||||||||||
| Diarrhea 2 | 7% | 8/116 | 1% | 1/78 | |||||||
Triglycerides1 (increase > 2.258 mmol/L) | 19% | 19/102* | 7% | 5/72* | |||||||
| Hemoglobin in urine1 | 6% | 6/102* | 3% | 2/72* | |||||||
Orthostatic Systolic Blood Pressure1 (decrease ≥ 20 mg Hg from supine to standing) | 8% | 9/116 | 1% | 1/78 | |||||||
| Age Group | Desvenlafaxine succinate | Placebo | ||||
| Ages 12-17 | ||||||
| Back/Flank pain 2 | 3% | 8/242 | 0% | 0/154 | ||
* Number of subjects with non-missing test result
1 Laboratory test or clinical measurement result
2 Reported MedDRA term
The risks associated with longer term desvenlafaxine succinate use were assessed in 6-month, open-label extension studies in pediatric patients (7 to 17 years of age) with MDD. In the total desvenlafaxine succinate-exposed population, the frequency of weight loss ≥ 3.5% was 23% (156 /684), with persistence of weight loss at study end in approximately 22% of these cases (35/156).
The long-term safety, including effects on growth, maturation and behavioural development in patients under 18 years of age has not been systematically evaluated.
Suicidality-Related Events:
In the desvenlafaxine pediatric studies, the totality of suicidality-related behaviours and ideation are captured by the Columbia Suicide Severity Rating Scale (C-SSRS), performed at all scheduled visits. The incidence rates below exclude events classified as “self-injurious behavior, no suicidal intent”.
In the two pooled, placebo-controlled 8 week studies, the incidence of suicidality-related events is 12.1% (28 /231) for placebo and 12.6% (45 /356) for desvenlafaxine succinate. In the 26- week, open-label extension studies that included the above trials, the incidence of suicidality-related events is 15.4% (105 /680).
The safety and efficacy of desvenlafaxine succinate in children under the age of 18 years have not been established and its use is not recommended.
Adverse Events Identified During Post-Approval Use
The following adverse events have been identified during post-approval use of desvenlafaxine succinate. Because post-approval reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency:
Cardiac Disorders: stress cardiomyopathy (Takotsubo cardiomyopathy)
Gastrointestinal – gastrointestinal bleeding, pancreatitis acute
Nervous System Disorder: serotonin syndrome
Skin and subcutaneous tissue disorders – Stevens-Johnson Syndrome, toxic epidermal necrolysis, erythema multiforme
DRUG INTERACTIONS
Overview
Selected drug interaction studies were performed. The combination of linear pharmacokinetics, a simple metabolic profile without the potential for CYP polymorphism factors, weak interactions with selected probe substrates, and low protein binding results in a low potential for the interaction of desvenlafaxine with other prescribed medications.
Drug-Drug Interactions Monoamine Oxidase Inhibitors
Desvenlafaxine succinate is contraindicated in patients taking MAOIs. Desvenlafaxine succinate must not be used in combination with a monoamine oxidase inhibitor (MAOI), or within at least 14 days of discontinuing treatment with an MAOI. Based on the half-life of desvenlafaxine succinate, at least 7 days should be allowed after stopping desvenlafaxine succinate before starting an MAOI (see CONTRAINDICATIONS).
Serotonin Syndrome
As with other serotonergic agents, serotonin syndrome, a potentially life-threatening condition, may occur with desvenlafaxine treatment, particularly with concomitant use of other agents that may affect the serotonergic neurotransmitter system (including triptans, SSRIs, other SNRIs, amphetamines, lithium, sibutramine, fentanyl and its analogues, dextromethorphan, tramadol, tapentadol, meperidine, methadone and pentazocine or St. John's Wort [Hypericum perforatum], with drugs which impair metabolism of serotonin (such as MAOIs, including linezolid [an antibiotic which is a reversible non-selective MAOI], and methylene blue; see CONTRAINDICATIONS), or with serotonin precursors (such as tryptophan supplements).
Serotonin syndrome symptoms may include mental status changes, autonomic instability, neuromuscular aberrations and/or gastrointestinal symptoms (see WARNINGS AND PRECAUTIONS).
If concomitant treatment of desvenlafaxine with an SSRI, an SNRI or a 5-hydroxytryptamine receptor agonist (triptan) is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases. The concomitant use of desvenlafaxine with serotonin precursors (such as tryptophan supplements) is not recommended.
Central Nervous System (CNS) Active Agents
The risk of using desvenlafaxine succinate in combination with other CNS-active drugs has not been systematically evaluated. Consequently, caution is advised when desvenlafaxine succinate is taken in combination with other CNS-active drugs.
Drugs Affecting Platelet Function (e.g., NSAIDs, ASA, and other anticoagulants)
Serious Drug Interactions
Monoamine Oxidase Inhibitors: See CONTRAINDICATIONS, and Drug-Drug interactions below.
Serotonin release by platelets plays an important role in hemostasis. Epidemiological studies of the case-control and cohort design that have demonstrated an association between use of psychotropic drugs that interfere with serotonin reuptake and the occurrence of upper gastrointestinal bleeding have also shown that concurrent use of an NSAID, ASA or other anticoagulants may potentiate this risk of bleeding.
Altered anticoagulant effects, including increased bleeding, have been reported when SSRIs or SNRIs are co-administered with warfarin. Patients receiving warfarin therapy should be carefully monitored when PRO-DESVENLAFAXINE is initiated or discontinued (see WARNINGS AND PRECAUTIONS, Hematologic, Abnormal Bleeding).
Potential for other drugs to affect desvenlafaxine succinate (see also ACTION AND CLINICAL PHARMACOLOGY)
Inhibitors of CYP3A4
CYP3A4 is a minor pathway for the metabolism of desvenlafaxine succinate. In a clinical study, ketoconazole (200 mg BID) increased the area under the concentration vs. time curve AUC of desvenlafaxine succinate (400 mg single dose) by about 43% and Cmax by about 8%.
Concomitant use of PRO-DESVENLAFAXINE with potent inhibitors of CYP3A4 may result in higher concentrations of desvenlafaxine succinate.
Inhibitors of other CYP enzymes
Based on in vitro data, drugs that inhibit CYP isozymes 1A1, 1A2, 2A6, 2D6, 2C8, 2C9, 2C19, and 2E1 are not expected to have significant impact on the pharmacokinetic profile of desvenlafaxine.
Potential for desvenlafaxine to affect other drugs (see also ACTION AND CLINICAL PHARMACOLOGY)
Drugs metabolized by CYP2D6
Clinical studies have shown that desvenlafaxine does not have a clinically relevant effect on CYP2D6 metabolism at the dose of 100 mg daily. When desvenlafaxine succinate was administered at a dose of 100 mg daily in conjunction with a single 50 mg dose of desipramine, a CYP2D6 substrate, the AUC of desipramine increased approximately 17%. When 400 mg of desvenlafaxine was administered (8 times the recommended 50 mg dose), the AUC of desipramine increased approximately 90%. When desvenlafaxine succinate was administered at a dose of 100 mg daily in conjunction with a single 60 mg dose of codeine, a CYP2D6 substrate metabolized to morphine, the AUC of codeine was unchanged, the AUC of morphine decreased approximately 8%. Concomitant use of desvenlafaxine with a drug metabolized by CYP2D6 may result in increased concentrations of that drug and decreased concentrations of its CYP2D6 metabolites.
Drugs metabolized by CYP3A4
In vitro, desvenlafaxine does not inhibit or induce the CYP3A4 isozyme. In a clinical study, desvenlafaxine (400 mg daily) was co-administered with a single 4 mg dose of midazolam (a CYP3A4 substrate). The AUC and Cmax of midazolam decreased by approximately 31% and 16%, respectively. In a second study, desvenlafaxine 50 mg daily was co-administered with a single 4 mg dose of midazolam. The AUC and Cmax of midazolam decreased by approximately
29% and 14%, respectively. Concomitant use of desvenlafaxine with a drug metabolized by CYP3A4 may result in lower exposure to that drug.
Drugs metabolized by a combination of both CYP2D6 and CYP3A4
Clinical studies with aripiprazole and tamoxifen suggest that desvenlafaxine at twice the recommended dose (100 mg daily) does not have a clinically relevant effect on drugs metabolized by a combination of both CYP2D6 and CYP3A4 enzymes.
Desvenlafaxine succinate was studied at a dose of 100 mg daily in conjunction with a single 5 mg dose of aripiprazole, a CYP2D6 and CYP3A4 substrate metabolized to the active metabolite dehydroaripiprazole.
A single 40 mg dose of tamoxifen, which is metabolized to active metabolites 4-hydroxy- tamoxifen and endoxifen by CYP2D6 and CYP3A4, was also studied in conjunction with desvenlafaxine succinate (100 mg daily).
Drugs metabolized by CYP1A2, 2A6, 2C8, 2C9 and 2C19
In vitro, desvenlafaxine does not inhibit CYP1A2, 2A6, 2C8, 2C9, and 2C19 isozymes and would not be expected to affect the pharmacokinetics of drugs that are metabolized by these CYP isozymes.
Electroconvulsive Therapy
There are no clinical data establishing the risks and/or benefits of electroconvulsive therapy combined with desvenlafaxine succinate treatment for MDD.
P-glycoprotein transporter
In vitro, desvenlafaxine is not a substrate or an inhibitor for the P-glycoprotein transporter. The pharmacokinetics of desvenlafaxine are unlikely to be affected by drugs that inhibit the P- glycoprotein transporter and desvenlafaxine is not likely to affect the pharmacokinetics of drugs that are substrates of the P-glycoprotein transporter.
Drug-Food Interactions
Food does not alter the bioavailability of desvenlafaxine.
Drug-Herb Interactions
St. John’s Wort
In common with SSRI’s, pharmacodynamic interactions between desvenlafaxine succinate and the herbal remedy St. John’s Wort may occur and may result in an increase in undesirable effects (see DRUG INTERACTIONS, Serotonin Syndrome).
Drug-Laboratory Interactions
False positive urine immunoassay screening tests for phencyclidine (PCP) and amphetamine have been reported in patients taking desvenlafaxine succinate. This is due to lack of specificity of the screening tests. False positive test results may be expected for several days following discontinuation of PRO-DESVENLAFAXINE therapy. Confirmatory tests, such as gas chromatography/mass spectrometry, will distinguish desvenlafaxine succinate from PCP and amphetamine.
Drug-Lifestyle Interactions
Ethanol
As with all CNS-active drugs, patients should be advised to avoid alcohol consumption while taking PRO-DESVENLAFAXINE.
Interference with Cognitive and Motor Performance
A clinical study that assessed the effects of desvenlafaxine on behavioral performance of healthy individuals did not reveal clinically significant impairment of psychomotor, cognitive, or complex behavior performance. However, since any CNS-active drug may impair judgment, thinking, or motor skills, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that PRO-DESVENLAFAXINE therapy does not adversely affect their ability to engage in such activities.
DOSAGE AND ADMINISTRATION
General
PRO-DESVENLAFAXINE is not indicated for use in children under 18 years of age (see WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
Recommended Dose and Dosage Adjustment
Initial Treatment
The recommended starting dose of PRO-DESVENLAFAXINE (desvenlafaxine succinate extended- release tablets) is 50 mg once daily, with or without food. In clinical studies, no additional benefit was demonstrated at doses greater than 50 mg/day. If the physician, based on clinical judgment, decides a dose increase above 50 mg/day is warranted for an individual patient, the maximum recommended dose should not exceed 100 mg/day. In clinical studies, doses of 50-400 mg/day were shown to be effective, although no additional benefit was demonstrated at doses greater than 50 mg/day, and adverse events and discontinuations were more frequent at higher doses. Patients should be periodically reassessed to determine the need for continued treatment.
Maintenance/Continuation/Extended Treatment
It is generally agreed that acute episodes of major depression require several months or longer of sustained pharmacologic therapy beyond response to the acute episode. Long-term efficacy of desvenlafaxine succinate (50 daily) for up to 26 weeks, following response during 20 weeks of acute, open-label treatment, was established in a placebo-controlled trial. Patients should be periodically reassessed to determine the need for maintenance treatment.
It is recommended that PRO-DESVENLAFAXINE be taken at approximately the same time each day.
PRO-DESVENLAFAXINE must be swallowed whole with liquids, and must not be chewed, divided or crushed. The medication is contained within a non-absorbable shell designed to release the drug at a controlled rate. The tablet shell, along with insoluble core components, is eliminated from the body; patients should not be concerned if they occasionally notice something that looks like a tablet in their stool. Due to the controlled-release design, PRO-
DESVENLAFAXINE should only be used in patients who are able to swallow the tablets whole.
Missed Dose
A patient missing a dose should take it as soon as they remember to. If it is almost time for the next dose, the missed dose should be skipped. The patient should be cautioned against taking two doses concomitantly to “make up” for the missed dose.
Discontinuing PRO-DESVENLAFAXINE
Symptoms associated with discontinuation of PRO-DESVENLAFAXINE, other SNRIs and SSRIs have been reported (see WARNINGS AND PRECAUTIONS, Discontinuation Symptoms and ADVERSE REACTIONS, Discontinuation symptoms). Patients should be monitored for these symptoms when discontinuing treatment. A gradual reduction in the dose rather than abrupt cessation is recommended. If intolerable symptoms occur following a decrease in the dose or upon discontinuation of treatment, then resuming the previously prescribed dose may be considered. Subsequently, the physician may continue decreasing the dose, but at a more gradual rate. In some patients, discontinuation may need to occur over periods of months or longer.
Switching Patients from Other Antidepressants to PRO-DESVENLAFAXINE
Discontinuation symptoms have been reported when switching patients from other antidepressants, including venlafaxine, to desvenlafaxine succinate. Tapering of the initial antidepressant may be necessary to minimize discontinuation symptoms (see CONTRAINDICATIONS).
Switching Patients to or from a Monoamine Oxidase Inhibitor
At least 14 days should elapse between discontinuation of an MAOI and initiation of therapy with PRO-DESVENLAFAXINE. In addition, based on the half-life of desvenlafaxine succinate, at least 7 days should be allowed after stopping desvenlafaxine succinate before starting an MAOI.
Use of PRO-DESVENLAFAXINE with Reversible MAOIs such as Linezolid or Methylene Blue
Do not start PRO-DESVENLAFAXINE in a patient who is being treated with a reversible MAOI such as linezolid or in whom intravenous methylene blue has been administered because there is increased risk of serotonin syndrome (see CONTRAINDICATIONS). In a patient who requires more urgent treatment of a psychiatric condition, non-pharmacological interventions, including hospitalization, should be considered.
In some cases, a patient already receiving PRO-DESVENLAFAXINE therapy may require urgent treatment with linezolid or intravenous methylene blue. If acceptable alternatives to linezolid or intravenous methylene blue treatment are not available and the potential benefits of linezolid or intravenous methylene blue are judged to outweigh the risks of serotonin syndrome in a particular patient, PRO-DESVENLAFAXINE should be stopped promptly, and linezolid or intravenous methylene blue can be administered. The patient should be monitored for symptoms of serotonin syndrome for two weeks or until 24 hours after the last dose of linezolid or intravenous methylene blue, whichever comes first (see WARNINGS AND PRECAUTIONS). Therapy with PRO-DESVENLAFAXINE may be resumed 24 hours after the last dose of linezolid or intravenous methylene blue.
Dosing Considerations
Patients with severe renal impairment and end-stage renal disease
The recommended dose in patients with severe renal impairment (24-hr CrCl < 30 mL/min) or end-stage renal disease (ESRD) is 50 mg every other day. Because of individual variability in clearance in these patients, individualization of dosage may be desirable. Supplemental doses should not be given to patients after dialysis (see ACTION AND CLINICAL PHARMACOLOGY, Renal Insufficiency).
Use in patients with hepatic impairment
No dosage adjustment is necessary for patients with hepatic impairment (see ACTION AND CLINICAL PHARMACOLOGY, Hepatic Insufficiency).
Geriatrics (≥ 65 years of age)
No dosage adjustment is required solely on the basis of age; however, possible reduced clearance of desvenlafaxine succinate should be considered when determining dose (see ACTION AND CLINICAL PHARMACOLOGY, Geriatrics).
Pediatrics
PRO-DESVENLAFAXINE is not indicated for use in children under the age of 18. Two placebo-controlled studies in 587 pediatric patients 7 to 17 years of age with MDD failed to demonstrate efficacy; neither short term, placebo-controlled study demonstrated statistically or clinically significant differences between desvenlafaxine succinate and placebo (see WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm; ACTION AND CLINICAL PHARMACOLOGY, Pediatrics).
Discontinuation of Therapy
A gradual reduction in the dose rather than abrupt cessation is recommended whenever possible. Discontinuation regimens should take into account the individual circumstances of the patient, such as duration of treatment and dose at discontinuation (see WARNINGS AND PRECAUTIONS and ADVERSE REACTIONS).
OVERDOSAGE
Human Experience
There is limited clinical experience with desvenlafaxine succinate overdosage in humans. In pre- marketing clinical trials, no cases of fatal acute overdose of desvenlafaxine succinate were reported.
Among the patients included in the pre-marketing major depressive disorder trials of desvenlafaxine succinate, there were four adults who ingested doses over 800 mg of desvenlafaxine (4000 mg [desvenlafaxine alone], 900, 1800 and 5200 mg [in combination with other drugs]); all patients recovered. In addition, a patient’s 11 month-old child accidentally ingested 600 mg of desvenlafaxine, was treated and recovered.
The adverse reactions reported within 5 days of an overdose > 600 mg that were possibly related to desvenlafaxine included: headache, vomiting, agitation, dizziness, nausea, constipation, diarrhea, dry mouth, paresthesia, and tachycardia.
Desvenlafaxine is the major active metabolite of venlafaxine. Overdose experience reported with venlafaxine (the parent drug of desvenlafaxine) is presented below; the identical information can be found in the Overdosage section of the venlafaxine Product Monograph.
Postmarketing Experience with EFFEXOR
In postmarketing experience, overdose with venlafaxine was reported predominantly in combination with alcohol and/or other drugs. The most commonly reported events in overdose include tachycardia, changes in level of consciousness (ranging from somnolence to coma), mydriasis, convulsion, and vomiting. Electrocardiographic changes (e.g., prolongation of QT interval, bundle branch block, QRS prolongation), ventricular tachycardia, bradycardia, hypotension, delayed rise in plasma creatine kinase levels, rhabdomyolysis, liver necrosis, serotonin syndrome, vertigo, and death have been reported. Muscle enzymes should be monitored in patients with venlafaxine overdose to detect development of rhabdomyolysis at an early stage and to initiate appropriate treatment. According to post-marketing overdose reports with venlafaxine (where overdose amounts were provided) fatal acute overdoses have been reported with venlafaxine alone at doses as low as approximately 1 gram.
Published retrospective studies report that venlafaxine overdosage may be associated with an increased risk of fatal outcomes compared to that observed with SSRI antidepressant products, but lower than that for tricyclic antidepressants. Epidemiological studies have shown that venlafaxine-treated patients have a higher burden of suicide risk factors than SSRI patients. The extent to which the finding of an increased risk of fatal outcomes can be attributed to the toxicity of venlafaxine in overdosage as opposed to some characteristics of venlafaxine-treated patients is not clear.
Prescriptions for PRO-DESVENLAFAXINE should be written for the smallest quantity of drug consistent with good patient management, in order to reduce the risk of overdose.
Management of Overdosage
Treatment should consist of those general measures employed in the management of overdosage with any SSRI/SNRI.
Induction of emesis is not recommended. Because of the moderate volume of distribution of this drug, forced diuresis, dialysis, hemoperfusion, and exchange transfusion are unlikely to be of benefit. No specific antidotes for desvenlafaxine are known.
Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm and vital signs. General supportive and symptomatic measures are also recommended. Gastric lavage with a large-bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion or in symptomatic patients. Activated charcoal should be administered.
In managing an overdose, consider the possibility of multiple drug involvement. The physician should consider contacting a poison control center for additional information on the treatment of any overdose.
ACTION AND CLINICAL PHARMACOLOGY
Mechanism of Action
Desvenlafaxine is the major active metabolite of venlafaxine which is also approved for treatment of depression. Preclinical studies have shown that desvenlafaxine succinate is a selective serotonin and norepinephrine reuptake inhibitor. The clinical efficacy of desvenlafaxine succinate is thought to be related to the potentiation of these neurotransmitters in the central nervous system.
Pharmacodynamics
Desvenlafaxine lacked significant affinity for numerous receptors, including muscarinic- cholinergic, H1-histaminergic, or α1-adrenergic receptors in vitro. Desvenlafaxine also lacked significant affinity for various ion channels, including calcium, chloride, potassium and sodium ion channels and also lacked monoamine oxidase (MAO) inhibitory activity. Desvenlafaxine lacked significant activity in the in vitro cardiac potassium channel (hERG) assay.
Pharmacokinetics
The single dose pharmacokinetics of desvenlafaxine are linear and dose-proportional in a dose range of 50 to 600 mg/day. The mean terminal half-life, t1/2, is approximately 11 hours. With once-daily dosing, steady-state plasma concentrations are achieved within approximately 4 - 5 days. At steady state, multiple-dose accumulation of desvenlafaxine is linear and predictable from the single-dose pharmacokinetic profile.
The pharmacokinetics of desvenlafaxine have been thoroughly evaluated in women and men. There are minimal differences based on gender; data from all subjects are presented below.
Absorption and Distribution:
The absolute oral bioavailability of desvenlafaxine succinate after oral administration is about 80%. Mean time to peak plasma concentrations (tmax) is about 7.5 hours after oral administration.
A food-effect study involving administration of desvenlafaxine succinate to healthy volunteers under fasting and fed conditions (high-fat meal) indicated that the Cmax was increased about 16% in the fed state, while the AUCs were similar. This difference is not clinically significant; therefore, PRO-DESVENLAFAXINE can be taken without regard to meals.
The plasma protein binding of desvenlafaxine is low (30%) and is independent of drug concentration. Desvenlafaxine’s volume of distribution at steady-state following intravenous administration is 3.4 L/kg, indicating distribution into nonvascular compartments.
Metabolism and Excretion:
Desvenlafaxine is primarily metabolized by conjugation (mediated by UGT isoforms) and, to a minor extent, through oxidative metabolism. CYP3A4 is the cytochrome P450 isozyme
For the management of suspected drug overdose, contact your regional Poison Control Centre.
mediating the oxidative metabolism (N-demethylation) of desvenlafaxine. Approximately 45% of desvenlafaxine is excreted unchanged in urine at 72 hours after oral administration.
Approximately 19% of the administered dose is excreted as the glucuronide metabolite and <5% as the oxidative metabolite (N,O-didesmethylvenlafaxine) in urine.
Residual Inert Matrix Tablet
Patients receiving PRO-DESVENLAFAXINE may notice an inert matrix tablet passing in the stool or via colostomy. Patients should be informed that the active medication has already been absorbed by the time the patient sees the inert matrix tablet.
Special Populations and Conditions Gender:
In a trial of healthy subjects administered doses up to of 300 mg, women had an approximately 25% higher Cmax and an approximately 10% higher AUC than age-matched men. No adjustment of dosage on the basis of gender is needed.
Pediatrics:
PRO-DESVENLAFAXINE is not indicated for use in children and adolescents.Two placebo controlled phase 3 studies in 587 pediatric patients 7 to 17 years of age with MDD failed to demonstrate efficacy; neither short term, placebo-controlled study demonstrated statistically or clinically significant differences between desvenlafaxine succinate and placebo (see also ADVERSE REACTIONS, Adverse Drug Reactions in Pediatrics (<18 years of age).
Phase 2 Pharmacokinetic Study
In a phase 2, 8-week open-label pharmacokinetic, safety, and tolerability study in 59 pediatric patients with MDD, desvenlafaxine succinate 10, 25, 50, and 100 mg was administered to 29 children (7 to 11 years old) and desvenlafaxine succinate 25, 50, 100, and 200 mg was administered to 30 adolescents (12 to 17 years old). Mean CL/F (apparent oral dose clearance) values were higher in children (range: 0.441 to 0.540 L/h/kg) than values obtained in 397 adults (mean ± SD: [0.31± 0.15 L/h/kg]). Mean CL/F values for adolescents (range: 0.282 to 0.441 L/hr/kg) were more comparable to CL/F values in adults. The effect of body weight on dose normalized AUC could be described by an exponential equation for each age group. Comparison of the predictions for AUC (normalized by dose) based on age and body weight or based only on body weight showed that body weight alone provides an adequate prediction for AUC. Mean urinary recovery of total desvenlafaxine and total N,O-didesmethylvenlafaxine ranged from 40% to 61% in children and 55 to 69% in adolescents. The pharmacokinetic results in pediatric patients from this study and the comparison with adults should be considered preliminary.
Twenty children and 20 adolescents who completed the pharmacokinetics study entered a 6- month, open-label, phase 2 extension safety study. The total daily dose of desvenlafaxine succinate was flexible between 10, 25, 50, and 100 mg for children, and between 25, 50, 100, and 200 mg for adolescents. Eighteen subjects (45%) completed the extension study.
In both studies combined, 28 subjects (70%) reported 1 or more treatment-emergent adverse event (TEAE). Four (20.0%) children and 3 (15.0%) adolescents reported adverse events that led to discontinuation of treatment: aggression (by 2 children), disturbance in attention and psychomotor hyperactivity (by 1 child), negativism (by 1 child) and nausea (by 1 adolescent), nausea and headache (by 1 adolescent), and pregnancy (by 1 adolescent). For children, the most common TEAEs during the on-therapy period of both studies combined were headache and abdominal pain reported by 3 (15.0%) and 3 (15.0%) of patients, respectively. For adolescents, the most common TEAEs during the on-therapy period of both studies combined were: somnolence, nausea, headache, and abdominal pain upper, reported by 6 (30.0%), 4 (20.0%), 3 (15.0%) and 3 (15.0%) of subjects, respectively. In addition, for child and adolescent subjects in the combined study population, post-baseline suicidal ideation occurred in 3 adolescents, as assessed via the Columbia Suicide Severity Rating Scale (C-SSRS). Suicidal ideation was reported in 1 adolescent subject who did not report suicidal ideation at the baseline C-SSRS assessment (the baseline C-SSRS assessment was the screening visit of the pharmacokinetic study) (see WARNINGS AND PRECAUTIONS, Potential Association with Behavioural and Emotional Changes, Including Self-Harm).
Geriatrics:
In a trial of healthy subjects administered doses of up to 300 mg, there was an approximate 32% increase in Cmax and a 55% increase in AUC in subjects older than 75 years of age (n =17), compared with subjects 18 to 45 years of age (n = 16). Subjects 65 to 75 years of age (n =15) had no change in Cmax but an approximately 32% increase in AUC, compared to subjects 18 to 45 years of age. No dosage adjustment is required solely on the basis of age; however, possible reduced renal clearance of desvenlafaxine should be considered when determining dose.
Race:
Pharmacokinetic analysis on the basis of race (White, N = 466; Black, N = 97; Hispanic, N = 39; Other, N =33) did not demonstrate an effect on the pharmacokinetics of desvenlafaxine succinate. No adjustment of dosage on the basis of race is needed.
Hepatic Insufficiency:
The disposition of desvenlafaxine succinate after administration of 100 mg was studied in subjects with mild (Child-Pugh A, n = 8), moderate (Child-Pugh B, n = 8), and severe (Child- Pugh C, n = 8) hepatic impairment and to healthy subjects (n = 12). Average AUC was increased by approximately 31% and 35% in patients with moderate and severe hepatic impairment, respectively, as compared to healthy subjects. Average AUC values were similar in subjects with mild hepatic impairment and healthy subjects (<5% difference). Systemic clearance (CL/F) was decreased by approximately 20% and 36% in patients with moderate and severe hepatic impairment, respectively, as compared to healthy subjects. CL/F values were comparable in mild hepatic impairment and healthy subjects (<5% difference).
The mean t1/2 changed from approximately 10 hours in healthy subjects and subjects with mild hepatic impairment to 13 and 14 hours in moderate and severe hepatic impairment, respectively. No dosage adjustment is necessary for patients with hepatic impairment.
Renal Insufficiency:
The disposition of desvenlafaxine after administration of 100 mg was studied in subjects with mild (n = 9), moderate (n = 8), severe (n = 7) and end-stage renal disease (ESRD) requiring dialysis (n = 9) and in healthy, age-matched control subjects (n = 8). Elimination was significantly correlated with creatinine clearance. Increases in AUCs of about 42% in mild renal impairment, about 56% in moderate renal impairment, about 108% in severe renal impairment, and about 116% in ESRD subjects were observed, compared with healthy, age-matched, control subjects.
The mean terminal half-life (t1/2) was prolonged from 11.1 hours in the control subjects to approximately 13.5, 15.5, 17.6, and 22.8 hours in mild, moderate, severe renal impairment and ESRD subjects, respectively. Less than 5% of the drug in the body was cleared during a standard 4-hour hemodialysis procedure. Therefore, supplemental doses should not be given to patients after dialysis.
Dosage adjustment is recommended in patients with significant impairment of renal function (see DOSAGE AND ADMINISTRATION, Patients with severe renal impairment and end-stage renal disease).
STORAGE AND STABILITY
Store at 15°C to 30°C.
SPECIAL HANDLING INSTRUCTIONS
None.
DOSAGE FORMS, COMPOSITION AND PACKAGING
PRO-DESVENLAFAXINE (desvenlafaxine extended-release tablets) contain 50 mg and 100 mg desvenlafaxine (free base) as desvenlafaxine succinate:
50 mg Tablet
Light pink colored, rounded square shaped, biconvex film-coated tablets, engraved with “APO” on one side and “DV” over “50” on the other side.
100 mg Tablet
Reddish orange colored, rounded square shaped, biconvex film-coated tablets, engraved with “APO” on one side and “DV” over “100” on the other side.
Inactive ingredients consist of colloidal silicon dioxide, hypromellose, magnesium stearate, microcrystalline cellulose, and film coating which consists of euroxide red iron oxide, polyethylene glycol, polyvinyl alcohol, red iron oxide (100 mg), talc, titanium dioxide, and yellow iron oxide (50 mg).
PRO-DESVENLAFAXINE 50 mg and 100 mg tablets are available in:
HDPE Bottles of 30, 100 and 500 tablets
Unit Dose Blisters of 100 (10 X 10) tablets
PART II: SCIENTIFIC INFORMATION PHARMACEUTICAL INFORMATION
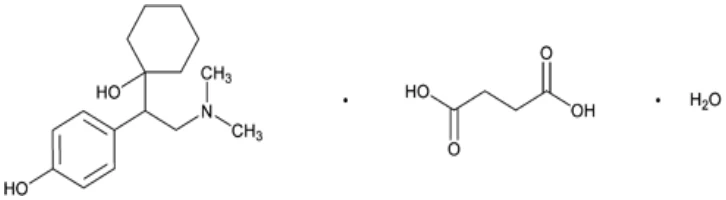
1 USP Dictionary
2 https://www.rsc.org/Merck- Index/monograph/m4207/desvenlafaxine%20derivative%20succinate%20monohydrate?q=authorize
| Drug Substance | |
| Common name: | Desvenlafaxine succinate monohydrate |
| Chemical name: | N,N-dimethyl-2-(1- hydroxycyclohexyl)-2-(4- hydroxyphenyl)ethylamine succinate monohydrate; 4-[2-(dimethylamino)-1-(1-hydroxycyclohexyl)ethyl]phenol succinate hydrate; 1-[(1RS)-2-(dimethylamino)-1-(4- hydroxyphenyl)ethyl]cyclohexanol hydrogen butanedioate monohydrate1 butanedioic acid, compound with 4-(2-(dimethylamino)-1-(1- hydroxycyclohexyl)ethyl)phenol (1:1) monohydrate1 |
| Molecular formula and molecular | |
| mass: | C16H25NO2•C4H6O4•H2O – [Desvenlafaxine Succinate |
| Monohydrate (anhydrous)]1,2 | |
| C16H25NO2 [Desvenlafaxine]2 | |
| 399.48 g/mol [Desvenlafaxine Succinate Monohydrate | |
| (anhydrous)] 1,2 | |
| 263.38 g/mol [Desvenlafaxine]2 | |
| Structural formula: | |
| Physicochemical properties: | Desvenlafaxine succinate monohydrate is a white to off-white powder that is soluble in water, freely soluble in methanol and slightly soluble in acetone and heptanes. |
| pH and pKa values | |
| pH | 4.67 (1% in H2O at 25°C) |
| pKa | pKa1: 8.34; pKa2: 10.11 |
CLINICAL TRIALS
Comparative Bioavailability Studies
Fasting Study – 50 mg
A single-dose, blinded, randomized, two-way, cross-over, comparative bioavailability study of PRO-DESVENLAFAXINE, 50 mg (Pro Doc Ltée.) and PRISTIQ® extended-release tablets, 50 mg (Pfizer Canada Inc.) was conducted in 48 healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 46 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Desvenlafaxine (1 x 50 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 2351.95 2518.37 (36) | 2221.94 2371.17 (35) | 105.9 | 96.9 – 115.6 |
AUCI (ng·h/mL) | 2383.20 2552.81 (36) | 2251.12 2402.74 (35) | 105.9 | 97.0 – 115.6 |
Cmax (ng/mL) | 98.52 100.98 (24) | 95.86 98.91 (26) | 102.8 | 97.2 – 108.7 |
Tmax3 (h) | 6.0 (2.0 – 18.0) | 7.0 (3.0 – 24.0) | ||
T½4 (h) | 9.35 (14) | 9.26 (13) | ||
1 PRO-DESVENLAFAXINE (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 50 mg (Pro Doc Ltée.)
2 PRISTIQ® (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 50 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
Fed Study – 50 mg
A single-dose, blinded, randomized, two-way, cross-over, comparative bioavailability study of PRO-DESVENLAFAXINE, 50 mg (Pro Doc Ltée.) and PRISTIQ® extended-release tablets, 50 mg (Pfizer Canada Inc.) was conducted in 24 healthy, adult, male subjects under high-fat, high-calorie fed conditions. Comparative bioavailability data from 22 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Desvenlafaxine (1 x 50 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 3427.52 3462.78 (14) | 3420.59 3460.48 (15) | 100.2 | 95.5 – 105.1 |
AUCI (ng·h/mL) | 3461.33 3497.49 (15) | 3457.72 3499.04 (15) | 100.1 | 95.4 – 105.0 |
Cmax (ng/mL) | 150.84 151.70 (11) | 147.62 148.34 (10) | 102.2 | 99.1 – 105.4 |
Tmax3 (h) | 9.0 (5.0 – 14.0) | 8.0 (5.0 – 14.0) | ||
T½4 (h) | 9.61 (8) | 9.60 (11) | ||
1 PRO-DESVENLAFAXINE (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 50 mg (Pro Doc Ltée.)
2 PRISTIQ® (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 50 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
Fasting Study – 100 mg
A single-dose, blinded, randomized, two-way, cross-over, comparative bioavailability study of PRO-DESVENLAFAXINE, 100 mg (Pro Doc Ltée.) and PRISTIQ® extended-release tablets, 100 mg (Pfizer Canada Inc.) was conducted in 41 healthy, adult, male subjects under fasting conditions. Comparative bioavailability data from 37 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Desvenlafaxine (1 x 100 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 5648.69 5904.73 (30) | 5352.25 5747.60 (34) | 105.5 | 96.2 − 115.8 |
AUCI (ng·h/mL) | 5770.81 6049.15 (31) | 5506.16 5937.18 (35) | 104.8 | 95.5 − 115.0 |
Cmax (ng/mL) | 243.16 248.50 (22) | 215.78 220.09 (19) | 112.7 | 105.1 − 120.8 |
Tmax3 (h) | 7.0 (3.0 – 18.0) | 6.0 (1.0 – 24.0) | ||
T½4 (h) | 9.24 (13) | 9.47 (14) | ||
1 PRO-DESVENLAFAXINE (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 100 mg (Pro Doc Ltée.)
2 PRISTIQ® (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 100 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
Fed Study – 100 mg
A single-dose, blinded, randomized, two-way, cross-over, comparative bioavailability study of PRO-DESVENLAFAXINE, 100 mg (Pro Doc Ltée.) and PRISTIQ® extended-release tablets, 100 mg (Pfizer Canada Inc.) was conducted in 24 healthy, adult, male subjects under high-fat, high-calorie fed conditions. Comparative bioavailability data from 24 subjects that were included in the statistical analysis are presented in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Desvenlafaxine (1 x 100 mg) Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means | 90% Confidence Interval |
AUCT (ng·h/mL) | 5386.58 5544.87 (23) | 5301.65 5471.14 (24) | 101.6 | 95.5 − 108.1 |
AUCI (ng·h/mL) | 5464.60 5629.28 (24) | 5381.94 5558.16 (24) | 101.5 | 95.4 − 108.1 |
Cmax (ng/mL) | 284.06 288.75 (19) | 263.79 267.14 (17) | 107.7 | 103.0 − 112.6 |
Tmax3 (h) | 6.0 (3.0 – 10.0) | 6.0 (4.0 – 11.0) | ||
T½4 (h) | 8.86 (8) | 8.70 (9) | ||
1 PRO-DESVENLAFAXINE (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 100 mg (Pro Doc Ltée.)
2 PRISTIQ® (desvenlafaxine as desvenlafaxine succinate) extended-release tablets, 100 mg (Pfizer Canada Inc.)
3 Expressed as median (range) only
4 Expressed as arithmetic mean (CV %) only
The efficacy of desvenlafaxine succinate for treatment of depression was established in four 8- week, randomized, double-blind, placebo-controlled, fixed-dose studies (at doses of 50 mg/day to 400 mg/day) in adult outpatients who met the Diagnostic and Statistical Manual of Mental Disorders (DSM-IV) criteria for major depressive disorder. In the first study, patients received 100 mg (n = 114), 200 mg (n = 116), or 400 mg (n = 113) of desvenlafaxine succinate once daily, or placebo (n = 118). In a second study, patients received either 200 mg (n = 121) or 400 mg (n = 124) of desvenlafaxine succinate once daily, or placebo (n = 124). In two additional studies, patients received 50 mg (n = 150 and n = 164) or 100 mg (n = 147 and n = 158) of desvenlafaxine succinate once daily, or placebo (n = 150 and n = 161).
The primary outcome measure in all studies was change in the 17-item Hamilton Rating Scale for Depression (HAM-D17) total score (LOCF Final). The main secondary outcome measure was overall improvement, as measured by the Clinical Global Impressions Scale – Improvement (CGI-I) (LOCF Final). Other secondary outcome measures included change in HAM-D17 total score (Observed Case and MMRM) and CGI-I (Observed Case) at week 8, as well as change in the Montgomery Asberg Depression Rating Scale (MADRS) score, change in the Sheehan Disability Scale (SDS) score, and the percentage of CGI-I responders, HAM-D17 responders, and HAM-D17 remissions. CGI-I responder was defined as a score of 1 (very much improved) or 2 (much improved), HAM- D17 responder was defined as ≥50% decrease from baseline HAM-D-17 total score, and remission was defined as HAM-D17 ≤ 7.
In these studies, the efficacy of desvenlafaxine succinate for treatment of depression was demonstrated by its superiority over placebo as measured by improvement on the primary outcome measure (HAM-D17) total score (LOCF) and the main secondary outcome measure (CGI-I) (LOCF). The results on the other secondary outcome measures were supportive of the positive primary and main secondary outcomes.
In studies directly comparing desvenlafaxine succinate doses of 50 mg/day and 100 mg/day, there was no suggestion of greater efficacy with the higher dose. Similarly in studies directly comparing desvenlafaxine succinate doses of 100 mg/day and 200 mg/day or 400 mg/day there was no suggestion of a greater efficacy with the higher doses [see DOSAGE AND ADMINISTRATION]. In contrast adverse events and discontinuations tended to be more frequent at higher doses (see Tables 1 through 5), although no severe toxicity was observed.
Long-Term Maintenance of Effect Studies
The efficacy of desvenlafaxine succinate in maintaining antidepressant effect was assessed in a long-term study.
In the long-term trial, adult outpatients meeting DSM-IV criteria for major depressive disorder, who responded to 8 weeks of open-label acute treatment with 50 mg/day desvenlafaxine succinate and subsequently remained stable for 12 weeks on desvenlafaxine succinate, were assigned randomly in a double-blind manner to remain on active treatment or switched to placebo for up to 26 weeks of observation for relapse. Response during the open phase was defined as a HAM-D17 total score of ≤ 11 and CGI-I ≤ 2 at the day 56 evaluation; stability was defined as not having a HAM-D17 total score of ≥ 16 at any office visit. Relapse during the double-blind phase was defined as follows: (1) a HAM-D17 total score of ≥ 16 at any office visit;
(2) discontinuation for unsatisfactory efficacy response; (3) hospitalized for depression; (4) suicide attempt; or (5) suicide. Patients receiving continued desvenlafaxine succinate treatment experienced statistically significantly longer time to relapse compared with placebo. At 26 weeks, the Kaplan-Meier estimated probability of relapse was 14% with desvenlafaxine succinate treatment versus 30% with placebo.
Secondary efficacy measures that supported the primary outcome included: HAM-D17 total score, remission based on HAM-D17, HAM-D6, and CGI-S scores.
DETAILED PHARMACOLOGY
Clinical Pharmacology Overview
The clearance of desvenlafaxine is uncomplicated, with glucuronidation and renal excretion of desvenlafaxine and its glucuronide being the major routes of elimination.
In vitro and in vivo studies suggest that there is low potential for clinically relevant pharmacokinetic interactions between desvenlafaxine and other prescribed medications. There was an increase in exposure in severe renally impaired patients.
Pharmacokinetic Profile
The pharmacokinetic profile of desvenlafaxine has been investigated in 23 phase 1 studies enrolling more than 652 healthy subjects and patients with hepatic or renal impairment.
Peak plasma concentrations are observed 6 to 10 hours after oral administration. Meals did not affect the bioavailability of desvenlafaxine. The plasma protein binding of desvenlafaxine in humans is low (approximately 30 %) and independent of drug concentration.
The clearance of desvenlafaxine is uncomplicated, with glucuronidation and renal excretion of desvenlafaxine (~45%) and its glucuronide metabolite (~19%) being the major routes of elimination. All metabolites of desvenlafaxine are accounted for in plasma and urine and are inactive. Only minor metabolism occurs through CYP3A4, and in vitro studies show no evidence for induction of the CYP3A4 enzyme pathway.
A study has been conducted to evaluate the effects of single doses of desvenlafaxine succinate and venlafaxine extended-release (ER) in subjects who had a genotype consistent with an extensive metabolizer (EM) or poor metabolizer (PM) CYP2D6 phenotype. There is no evidence to indicate that CYP2D6 isozymes contribute to the metabolism of desvenlafaxine, however, the metabolism of venlafaxine to desvenlafaxine is dependent on CYP2D6. Therefore, the metabolizer phenotype was expected to influence the pharmacokinetics of venlafaxine but not of desvenlafaxine. After administration of venlafaxine ER, significant differences were observed between EM and PM subjects in the pharmacokinetics of both venlafaxine and desvenlafaxine, resulting in much higher concentrations of venlafaxine and lower concentrations of desvenlafaxine in PM subjects compared with EM subjects. As expected, the CYP2D6 phenotype does not significantly alter the pharmacokinetics of desvenlafaxine after administration of desvenlafaxine succinate.
Hepatic and Renal Studies
In keeping with the predominant role of renal excretion, glomerular filtration as measured by creatinine clearance, is the major determinant of desvenlafaxine clearance. Increases in exposure to desvenlafaxine are observed as the degree of renal impairment increased in mild, moderate, and severe renal impairment, and end stage renal disease (ESRD). Changes in the pharmacokinetics of desvenlafaxine with increasing age are also largely due to decreasing renal function. As shown by minimal recovery of desvenlafaxine in dialysate fluid (<5% of administered dose of desvenlafaxine succinate), dialysis is not expected to have any impact on the pharmacokinetics of desvenlafaxine.
For subjects with mild, moderate, and severe hepatic impairment, as characterized by Child-Pugh A, B, and C categories (see ACTION AND CLINICAL PHARMACOLOGY, Hepatic Insufficiency), there was a trend for increased exposures as measured by area under the concentration-versus-time curve (AUC) and Cmax. Therefore, although hepatic metabolism is not the most important mechanism for removal of desvenlafaxine, as shown by decreased clearance in moderate and severe hepatic impairment, hepatic metabolism still plays an important role in elimination of desvenlafaxine.
Minor increases in Cmax and AUC were observed for women compared with men. Differences in pharmacokinetics due to race were not observed; the metabolism of desvenlafaxine does not utilize enzyme systems that are sensitive to polymorphic distributions in humans.
Drug Interactions
Based on in vitro data, drugs that inhibit CYP isozymes 1A1, 1A2, 2A6, 2D6, 2C8, 2C9, 2C19, and 2E1 are not expected to have significant impact on the pharmacokinetic profile of desvenlafaxine. Results of additional in vitro studies showed that desvenlafaxine does not inhibit CYP1A2, 2A6, 2C8, 2C9, 2C19 and CYP3A4 isozymes and would not be expected to affect the pharmacokinetics of drugs that are metabolized by these CYP isozymes.
Several drug interaction studies were performed with desvenlafaxine. Observed changes in desipramine pharmacokinetics (increases in AUC and Cmax), when desvenlafaxine succinate is administered concomitantly, indicate that desvenlafaxine is a weak inhibitor of the CYP2D6 isozyme. Coadministration of midazolam and desvenlafaxine succinate showed a minor decrease in the relative bioavailability of midazolam. In vitro studies ruled out that induction of CYP3A4 isozyme by desvenlafaxine was responsible for the observed changes. Finally, minor increases in desvenlafaxine exposure during concomitant administration with ketoconazole (a CYP3A4 inhibitor) predict that inhibition of the CYP3A4 metabolic pathway by other drugs would have a minor impact on the pharmacokinetics of desvenlafaxine. The combination of linear pharmacokinetics, a simple metabolic profile without the potential for CYP polymorphism factors, weak interactions with selected probe substrates, and low protein binding results in a low potential for the interaction of desvenlafaxine with other prescribed medications.
Population Pharmacokinetics
Population pharmacokinetic analyses were conducted to examine factors appropriate to the patient population. The results demonstrated that no dose adjustments are needed for patients receiving treatment with desvenlafaxine succinate based on the patient demographic characteristics (body weight, age, gender, and race) and concomitant medications taken.
Safety and Tolerability
Based on data from a thorough QT/QTc study, desvenlafaxine has a low potential to prolong QT interval.
Table 9: Estimated and 90% Confidence Interval for QTc Changes from Time-Matched Baseline Relative to Placebo at Hour 8 after Dose with Different Heart Rate Correctionsa
| Treatment | Fridericia’s QT Correction (ms) | Population QT Correction (ms) | ||
| Desvenlafaxine succinate 200 mgb | 1.5 (-0.88, 3.88) | 3.18 (0.87, 5.50) | ||
Desvenlafaxine succinate 600 mgb | -2.43 (-4.90, 0.04) | 0.98 (-1.42, 3.38) | ||
Moxifloxacin 400 mg (Active control) | 10.80 (8.44, 13.16) | 10.92 (8.62, 13.22) | ||
| ||||
Nonclinical Pharmacology
Desvenlafaxine succinate salt (DVS) has been developed as a sustained-release (SR) tablet for the treatment of major depressive disorder (MDD). It is a selective inhibitor of the human serotonin and norepinephrine monoamine transporters and is commonly refer to as an SNRI. Nonclinical studies have demonstrated that DVS acutely and dose-dependently increases serotonin (5-HT) and norepinephrine (NE) in the brain frontal cortex.
The nonclinical data indicate that DVS has a profile of in vitro and in vivo activities that demonstrate increases in 5-HT and NE levels that lead to efficacy in models of depression, anxiety and pain. The efficacy of DVS in models of depression is believed to be related to the potentiation of serotonergic and noradrenergic activity in the central nervous system (CNS). Characterization of DVS was done using in vitro assays to determine selectivity for the 5-HT and NE monoamine transporters. Desvenlafaxine was profiled at 10 µM for activity at 96 targets (i.e., receptors, transporters, enzymes, channels) by NovaScreen®. No significant activity was detected for any targets with the exception of the 5-HT and NE monoamine transporters.
Desvenlafaxine, by inhibiting the 5-HT and NE transporter, elevates rat cortical and hypothalamic levels of both 5-HT and NE, as measured using microdialysis techniques. These increased 5-HT and NE levels are also evident by the acute decreases observed in serotonergic and noradrenergic neuronal firing in rats that is due to stimulation of inhibitory cell body autoreceptors by 5-HT and NE, respectively. Desvenlafaxine produces a desensitization of rat pineal beta-mediated cAMP response due to the increase in NE caused by NE transporter blockage.
Desvenlafaxine was active in the 4-plate test paradigm in mice supporting anxiolytic activity and was active in several rodent models of depression. DVS was efficacious in rodent pain models, indicating antinociceptive activity.
Safety pharmacology studies conducted under the DVS SR development program, consisted of the core battery of safety pharmacology studies to evaluate the effects of a single oral dose on the CNS and respiratory system of rats and the cardiovascular system of dogs, as well as in vitro human ether a-go-go related gene (hERG) channel assays. Earlier studies, not conducted under Good Laboratory Practice (GLP) consisted of safety pharmacology studies on cardiovascular effects in dogs (in vitro Purkinje fiber electrophysiology and in vivo intracardiac conduction) and ancillary pharmacology studies on the effects on the CNS of mice and rats after a single intraperitoneal (IP) dose, on the respiratory system of guinea pigs after an intravenous (IV) dose, and in rats on the renal/urinary system, the gastrointestinal system, and glucose metabolism after a single oral dose.
In safety pharmacology studies in rats given a single oral gavage dosage of DVS at up to 1000 mg/kg, there were no toxicologically significant effects of desvenlafaxine on the CNS or respiratory system. While there was a dose-related decrease in respiratory rate, the mean values remained within published normal limits for rats.
Results of in vitro studies (hERG assays with DVS at concentrations up to 195 μM and its metabolite N,O-didesmethylvenlafaxine at a concentration of 10 μM, and a canine Purkinje fiber assay with desvenlafaxine fumarate salt at 10 μM) and an in vivo study (intracardiac conduction in dogs given desvenlafaxine butenedioate salt as a single IV dosage at up to 10 mg/kg) indicated that desvenlafaxine does not produce any effects on atrial or ventricular conduction, including conduction through the specialized ventricular conduction system or blockade of cardiac ion channels. In cardiovascular safety pharmacology studies, there were no effects on the electrocardiogram (ECG), including PR, QRS, and QTc intervals, of dogs given a single oral gavage dosage of DVS at up to 300 mg/kg or DVS SR tablets at 100 mg/kg. There were increases in the heart rate (HR) and mean arterial blood pressure (MABP) of dogs given DVS (100 and 300 mg/kg) or DVS SR tablets (100 mg/kg), and increases in the MABP of spontaneously hypertensive rats given a single oral dosage of desvenlafaxine free base (50 mg/kg); these changes were consistent with similar effects reported for some antidepressant agents in humans. In addition, in oral repeat-dose toxicity studies, there were no compound- related changes in the ECG, or macroscopic or microscopic changes in the hearts of dogs given desvenlafaxine free base at dosages up to 300 mg/kg for 3 months, DVS at dosages up to 50 mg/kg/day for 9 months or 100 mg/kg/day for 3 months, or DVS SR tablets at up to 400 mg/kg/day for 3 months.
In rats given a single oral dosage up to 30 mg/kg/day, desvenlafaxine produced no adverse effect on renal excretory function, no effect on gastric acid secretion or emptying, and no irritation to the gastrointestinal system. Desvenlafaxine had no effect on plasma glucose levels in fed or fasted rats after a single oral dosage of 30 mg/kg; however, in a glucose tolerance test in fasted rats, the peak plasma glucose level was significantly decreased at 30 mg/kg.
TOXICOLOGY
Toxicology Program
The principal toxicology studies included single-dose and repeat-dose studies in rats and dogs; genetic toxicology studies; 2-year carcinogenicity studies in mice and rats; and reproductive and developmental studies in rats and rabbits. Special studies were conducted to define target organ toxicity, to evaluate the gastrointestinal tolerability of the sustained release (SR) tablets that were used in clinical trials, and to further evaluate the effects of desvenlafaxine on fertility in male and female rats.
Single-Dose
A single oral dosage of desvenlafaxine (salt form) resulted in death at ≥ 1800 mg/kg in mice and
≥ 2500 mg/kg in rats. A single IP dosage of desvenlafaxine (salt form) resulted in death at ≥ 250 mg/kg in mice. A single IP dosage of DVS resulted in death at ≥ 700 mg/kg in rats. There was no mortality in dogs given a single oral dosage of desvenlafaxine (salt form) at up to 500 mg/kg.
Repeat-Dose
Rats
In the 1-month toxicity study in rats, the no-observed-adverse-effect level (NOAEL) was 675 mg/kg/day (the highest dosage), based on no toxicologically significant effects at any dosage. In the 3-month toxicity study in rats, the NOAEL was 100 mg/kg/day, based on mortality and decreased food consumption at 1000 mg/kg/day, and increased salivation and decreased body weights and body-weight gains at ≥ 500 mg/kg/day. In the 6-month toxicity study in rats, the NOAEL was 100 mg/kg/day in males (based on decreases in body weight in males at 300 mg/kg/day) and 300 mg/kg/day in females (the highest dosage administered).
Dogs
In the 1-month toxicity study in dogs, the NOAEL was 175 mg/kg/day (the highest dosage), based on no toxicologically significant effects at any dosage. In the 3-month toxicity study in dogs, the NOAEL was 100 mg/kg/day, based on mortality and decreased body weights at 300 mg/kg/day and central nervous system (CNS)-related clinical observations (chorea-like movements, stereotypy, and convulsions as early as week 1) at 200 and 300 mg/kg/day. Because the target organ toxicity was not identified in this 3-month study, two (2) additional 3-month studies were conducted at higher dosages (oral gavage, up to 500 mg/kg/day; SR tablets up to 400 mg/kg/day). These 2 additional 3-month studies demonstrated the CNS to be the target organ based on clinical signs and the NOAEL was 100 mg/kg/day and 200 mg/kg/day in the oral gavage and SR tablet studies, respectively. In the 9-month toxicity study in dogs, the NOAEL was 50 mg/kg/day (the highest dosage), based on no adverse effects at any dosage.
Carcinogenesis
Desvenlafaxine succinate administered by oral gavage to mice and rats for 2 years did not increase the incidence of tumors in either study.
Mice
Mice received desvenlafaxine at dosages up to 500/300 mg/kg/day (dosage lowered after 45 weeks of dosing). The 300 mg/kg/day dose was 180 times on a mg/kg basis, the maximum recommended human dose (MRHD) of 100 mg/day, and 15 times the MRHD on a mg/m2 basis.
Rats
Rats received desvenlafaxine at dosages up to 300 mg/kg/day (males) or 500 mg/kg/day (females). The highest dose was 180 (males) or 300 (females) times, on a mg/kg basis the MRHD of 100 mg/day, and 29 (males) or 48 (females) times the MRHD of 100 mg/day, on a mg/m2 basis.
Mutagenesis
Desvenlafaxine was not genotoxic in the in vitro bacterial mutation assay (Ames test) and was not clastogenic in an in vitro chromosome aberration assay in cultured CHO cells, an in vivo mouse micronucleus assay, or an in vivo chromosome aberration assay in rats. Additionally, desvenlafaxine was not genotoxic in the in vitro CHO mammalian cell forward mutation assay and was negative in the in vitro BALB/c-3T3 mouse embryo cell transformation assay.
Impairment of Fertility
Reduced fertility was observed in a study in which both male and female rats received desvenlafaxine. This effect was noted at oral doses approximately 60 times, on a mg/kg basis, and 10 times the maximum human dose (MRHD) of 100 mg/day on a mg/m2 basis. There was no effect on fertility at oral doses approximately 18 times the MRHD on a mg/kg basis and 3 times the MRHD on a mg/m2 basis. The human relevance of this finding is unknown.
Teratogenicity
When desvenlafaxine was administered orally to pregnant rats and rabbits during the period of organogenesis, there was no evidence of teratogenicity in rats at any doses tested, up to 60 times on a mg/kg basis and up to 10 times the maximum recommended human dose (MRHD) of 100 mg/day (on a mg/m2 basis) in rats. In rabbits, there was no evidence of teratogenicity at doses up to 45 times (on a mg/kg basis) the MRHD of 100 mg/day, or 15 times the MRHD (on a mg/m2 basis). However, fetal weights were decreased in rats with a no effect dose 60 times the MRHD (on a mg/kg basis) and 10 times the MRHD (on a mg/m2 basis).
Reproductive Toxicology
When administered orally to pregnant rats throughout gestation and lactation and continued through weaning, desvenlafaxine has been shown to cause decrease in fetal weights, decrease in pup weights and increase in pup deaths when given in doses 180 times the human dose of 100 mg/day on a mg/kg basis, and 29 times on a mg/m2 basis. Post-weaning growth and reproductive performance of the progeny were not affected by maternal treatment with desvenlafaxine.
Juvenile Animal Studies
In a juvenile animal study, male and female rats were treated with desvenlafaxine (75, 225 and 675 mg/kg/day) starting on postnatal day (PND) 22 through 112. Behavioral deficits (longer time immobile in a motor activity test, longer time swimming in a straight channel test, and lack of habituation in an acoustic startle test) were observed in males and females but were reversed after a recovery period. A No Adverse Effect Level (NOAEL) was not identified for these deficits. The Low Adverse Effect Level (LOAEL) was 75 mg/kg/day which was associated with plasma exposure (AUC) twice the levels measured with a pediatric dose of 100 mg/day. In a second juvenile animal study, male and female rats were administered desvenlafaxine (75, 225 or 675 mg/kg/day) for 8-9 weeks starting on PND 22 and were mated with naïve counterparts.
Delays in sexual maturation and decreased fertility, number of implantation sites and total live embryos were observed in treated females at all doses. The LOAEL for these findings is 75 mg/kg/day which was associated with an AUC twice the levels measured with a pediatric dose of 100 mg/day. These findings were reversed at the end of a 4-week recovery period. The relevance of these findings to humans is not known.
REFERENCES
- 1. Akiskal HS, Benazzi F, Perugi G, Rihmer Z. Agitated "unipolar" depression re- conceptualized as a depressive mixed state: Implications for the antidepressant-suicide controversy. J Affect Disord. 2005; 85:245-58.
- 2. Boyer EW, Shannon M. The Serotonin Syndrome. N Engl J Med. 2005; 352:1112-20.
- 3. Boyer P, Montgomery S, Lepola U, Germain JM, Brisard C, Ganguly R. et al. Efficacy, safety, and tolerability of fixed-dose desvenlafaxine 50 and 100 mg/day for major depressive disorder in a placebo-controlled trial. Int. Clin. Psychopharmacology 2008; 23(5): 243-253.
- 4. Culpepper L, Davidson JRT, Dietrich AJ, Goodman WK, Kroenke K, Schwenk TL. Suicidality as a Possible Side Effect of Antidepressant Treatment. J Clin Psychiatry. 2004; 6(2):78-88.
- 5. DeMartinis NA, Yeung PP, Entsuah R, Manley AL. A Double-Blind, Placebo- Controlled Study of the Efficacy and Safety of Desvenlafaxine Succinate in the treatment of Major Depressive Disorder. J Clin Psychiatry 2007; 68 (5): 677-688.
- 6. Haddad PM. Antidepressant discontinuation syndromes. Drug Saf. 2001; 24(3):183-97.
- 7. Illett KF, Hackett LP, Dusci LJ, Roberts MJ, Kristensen JH, Paech J, et al. Distribution and excretion of venlafaxine and O-desmethylvenlafaxine in human milk. Br J Clin Pharmacol. 1998; 45:459-62.
- 8. Liebowitz MR, Manley AL, Padmanabhan SK, Ganguly R, Tummala R, Tourian KA. Efficacy, safety, and tolerability of desvenlafaxine 50 mg/day and 100 mg/day in outpatients with major depressive disorder. Curr Med Res and Opin 2008; 24(7): 1877- 1890
- 9. Millan MJ. The role of monoamines in the actions of established and novel antidepressant agents: a critical review. Eur J Pharmacol. 2004; 500:371-84.
- 10. Rosenthal JZ, Boyer P, Vialet C, Hwang E, Tourian K. Efficacy and safety of desvenlafaxine 50 mg/d for prevention of relapse in major depressive disorder: A randomized controlled trial. J Clin Psychiatry. 2013; 74:2.
- 11. Product Monograph- PRISTIQ® (desvenlafaxine succinate extended-release tablets) 50 mg and 100 mg. Pfizer Canada Inc., Submission Control No: 225933, Date of Revision: February 5, 2020.