


Product Monograph - Trazodone-50
INDICATIONS AND CLINICAL USE
TRAZODONE (trazodone hydrochloride) is of value in the symptomatic relief of depressive illness.
CONTRAINDICATIONS
TRAZODONE (trazodone hydrochloride) is contraindicated in patients with a known hypersensitivity to trazodone.
WARNINGS
Priapism has occurred with the use of trazodone. Surgical intervention was required in approximately 1/3 of the cases reported and permanent impairment of erectile function or impotence resulted in a portion of these cases. Male patients should immediately discontinue the drug and consult their physician if prolonged or inappropriate erections occur. It would be advisable for the treating physician to consult an urologist or appropriate specialist if the condition persists for more than 24 hours in order to decide on a management approach.
Recent clinical studies have shown that trazodone hydrochloride may be arrhythmogenic in some patients with pre-existing cardiac disease. Isolated PVC's, ventricular couplets, and in two patients, short episodes (3 to 4 beats) of ventricular tachycardia are the identified arrhythmias. Several post-marketing reports of arrhythmias exist in trazodone-treated patients; in both those patients with pre-existing cardiac disease and in some patients who did not have pre-existing cardiac disease. Therefore, patients with pre-existing cardiac disease should be closely monitored, particularly for cardiac arrhythmias until the results of prospective studies are available. TRAZODONE (trazodone hydrochloride) is not recommended for use during the initial recovery phase of myocardial infarction.
Angle-Closure Glaucoma
As with other antidepressants, TRAZODONE can cause mydriasis, which may trigger an angle closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
PRECAUTIONS
General: As the possibility of suicide in depressed patients remains during treatment and until significant remission occurs, patients with suicide ideation should never have access to large quantities of trazodone; therefore, the number of tablets prescribed at any one time should take this possibility into account.
In a small number of patients, episodes of grand mal seizures have been reported. Most of these patients were already receiving anticonvulsant therapy for a previously diagnosed seizure disorder.
Safety of Driving: TRAZODONE (trazodone hydrochloride) may impair the mental and/or physical abilities required for performance of potentially hazardous tasks, such as operating automobile or dangerous machinery. Therefore, the patient should be cautioned against engaging in such activities while impaired.
Interactions: The response to alcohol and the effects of barbiturates and other CNS depressants may be enhanced by trazodone; patients should be cautioned accordingly.
Serum phenytoin and digoxin levels have been reportedly increased in patients receiving trazodone concurrently with either of these two drugs. TRAZODONE should be discontinued for as long as clinically feasible prior to elective surgery since little is known about the interaction between trazodone and general anesthetics.
Administration of TRAZODONE should be initiated very cautiously with gradual increase in dosage as required if a MAO inhibitor is given concomitantly or has been discontinued shortly before medication with TRAZODONE is instituted, because it is not known whether an interaction will occur between TRAZODONE and MAO inhibitors.
Caution is required if TRAZODONE is given to patients receiving antihypertensive drugs, and an adjustment in the dose of antihypertensive medication may be required since trazodone may cause hypotension, including orthostatic hypotension and syncope.
Concurrent administration of electroshock therapy should be avoided because of the absence of experience.
Use in Pregnancy and Nursing Mothers: TRAZODONE it should not be used in women of child-bearing potential unless, in the opinion of the physician, the expected benefits justify the potential risk to the fetus, because the safety and use of trazodone in pregnant women have not been established.
Unless the potential benefits justify the possible risks to the child, TRAZODONE should not be administered to nursing mothers since trazodone and/or its metabolites have been detected in the milk of lactating animals.
Use in Children: In children below the age of 18, the safety and effectiveness of trazodone have not been established.
Laboratory Tests: In patients who develop sore throat, fever or other signs of infection or blood dyscrasia, it is recommended that white blood cell and differential count falls be performed. If the white blood cell or absolute neutrophil count falls below normal, TRAZODONE should be discontinued.
Hyperprolactinemia and Breast Tumours: Sufficient experimental evidence exists to conclude that the chronic administration of those psychotropic drugs, such as trazodone, which increase prolactin secretion has the potential to induce mammary neoplasms in rodents under appropriate conditions. It is indicated in tissue culture experiments that approximately one-third of human breast cancers are prolactin dependent in vitro, a factor of potential importance if the prescription of these drugs is contemplated in a patient with a previously detected breast cancer.
Disturbances such as galactorrhea, amenorrhea, gynecomastia and impotence have been reported, but the clinical significance of elevated serum prolactin levels or increased secretion and turnover are unknown for most patients. An association between the chronic administration of these drugs and mammary tumorigenesis has not been found in clinical studies or epidemiologic studies conducted to date. ; available evidence is considered too limited to be conclusive at this time (see TOXICOLOGY).
ADVERSE REACTIONS
Drowsiness, nausea/vomiting, headache and dry mouth are the most common adverse reactions encountered. Adverse reactions reported include the following:
Behavioural: drowsiness, fatigue, lethargy, retardation, lightheadedness, dizziness, difficulty in concentration, confusion, impaired memory, disorientation, excitement, agitation, anxiety, tension, nervousness, restlessness, insomnia, nightmares, anger, hostility, and, rarely, hypomania, visual distortions, hallucinations, delusions and paranoia.
Neurologic: tremor, headache, ataxia, akathisia, muscle stiffness, slurred speech, retarded speech, vertigo, tinnitus, tingling of extremities, paresthesia, weakness, grand mal seizures (see PRECAUTIONS) and, rarely, impaired speech, muscle twitching, numbness, dystonia and involuntary movements.
Autonomic: dry mouth, blurred vision, diplopia, miosis, nasal congestion, constipation, sweating, urinary retention, increased urinary frequency, and incontinence.
Cardiovascular: orthostatic hypotension, hypertension, tachycardia, palpitations, shortness of breath, apnea, syncope, arrhythmias, prolonged PR interval, atrial fibrillation, bradycardia, ventricular ectopic activity (including ventricular tachycardia), myocardial infarction, and cardiac arrest.
Gastrointestinal: nausea, vomiting, diarrhea, gastrointestinal discomfort, anorexia and increased appetite.
Endocrine: priapism (See WARNINGS), decrease and, more rarely, increase in libido, weight gain and loss, and, rarely, menstrual irregularities, retrograde ejaculation, and inhibition of ejaculation.
Allergic or Toxic: skin rash, itching, edema, and, rarely, hemolytic anemia, methemoglobinemia, liver enzyme alterations and obstructive jaundice, leukocytoclastic vasculitis, purpuric maculopapular eruptions, photosensitivity and fever.
Miscellaneous: aching joints and muscles, peculiar taste, hypersalivation, chest pain, hematuria, red, tired and itchy eyes.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
TRAZODONE (trazodone hydrochloride) overdosage may cause an increase in the incidence or severity of any of the reported adverse reactions, e.g. hypotension and excessive sedation. In one known suicide attempt, symptoms of drowsiness and weakness were apparent three hours after the ingestion of 7.5 grams (12.5 times the maximum daily dose) of trazodone hydrochloride. This patient recovered uneventfully. To date, there have been no reports of death by deliberate or accidental overdosage with trazodone alone.
As no specific antidote for trazodone hydrochloride exists, management of overdosage should be symptomatic and supportive.
A patient should be admitted to the hospital as soon as possible and the stomach emptied by gastric lavage if ingestion of an overdosage is suspected. In facilitating elimination of the drug, forced diuresis may be useful.
DOSAGE AND ADMINISTRATION
Dosage should be initiated at a low level and increased gradually. The clinical response and any evidence of intolerability should be carefully noted. It should be kept in mind that there may be a lag in therapeutic response and that increasing the dosage rapidly does not normally shorten this latent period but may increase the incidence of side effects.
Usual Adult Dosage: The recommended initial dose is 150 to 200 mg a day, in two or three divided doses. In order to reduce the incidence of adverse reactions, TRAZODONE (trazodone hydrochloride) should be taken shortly after a meal or light snack. The initial dose may be increased by increments of 50 mg, usually up to 300 mg daily in divided doses, according to tolerance and response. Doses up to 400 mg daily and, rarely, up to 600 mg daily in hospitalized patients, may be required in some patients. The administration of a major portion of the daily dose at bedtime or a reduction of dosage may be required in the event that drowsiness occurs.
The dosage may be gradually reduced once an adequate response has been achieved with adjustment depending on therapeutic response. The dosage should be kept at the lowest effective level during prolonged maintenance therapy.
Use in the Elderly: Doses not exceeding half of the recommended adult dosage should be used in the elderly, with adjustments made depending on tolerance and response.
TRAZODONE is not recommended in the pediatric age group because safety and effectiveness in children have not been established.
PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: trazodone hydrochloride
Chemical Name: 2-[3-[4-(m-chlorophenyl)-1-piperazinyl]-propy]-s-triazolo-[4,3-a]-pyridin-3(2H)- one monohydrochloride
Structural Formula:
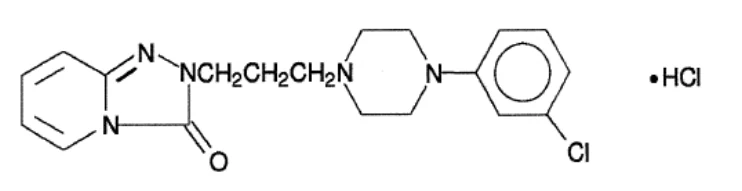
Molecular Formula: C19H22ClN5O∙HCI
Molecular Weight: 408.33 g/mol
Description: Trazodone hydrochloride is a white to off-white odourless crystalline powder which is sparingly soluble in chloroform and in water. It melts between 231° and 234° when the melting point determination is carried out in an evacuated capillary tube; otherwise, it melts with decomposition over a broad range below 230°.
Composition
In addition to trazodone hydrochloride, each tablet contains the non-medicinal ingredients colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose, sodium lauryl sulfate, sodium starch glycolate, and starch . The 50 and 150 mg tablets also contain FD&C yellow #6.
Stability and Storage Recommendations
Store at controlled room temperature 15°C to 30°C. Protect from light.
AVAILABILITY OF DOSAGE FORMS
TRAZODONE-50 TABLETS 50 mg
Pale orange, round, biconvex tablet. Scored and engraved APO over T50 on one side, other side plain. Available in bottles of 100 and 250 tablets.
TRAZODONE-100 TABLETS 100 mg
White to off white, round, biconvex tablet. Scored and engraved APO over T100 on one side, other side plain. Available in bottles of 100 and 500 tablets.
TRAZODONE-150 D TABLETS 150 mg
Pale orange, flat-faced, radial-edged, rectangular tablets, engraved 50 over score 25 over score 25 over score 50 on one side, other side engraved APO-150. Available in bottles of 100.
The design of the TRAZODONE-150 D tablet makes dosage adjustments easy. 150 mg strength:
Each tablet can be broken accurately to provide any of the following dosages:

50 mg (one-third of a tablet)
75 mg (one-half of a tablet)
100 mg (two-thirds of a tablet)
150 mg (the entire tablet)
Instructions: To break the TRAZODONE-150 D tablet accurately and easily hold the tablet between your thumb and index fingers close to the appropriate tablet score (groove). Then with the tablet score facing you, apply pressure and snap the tablet segments apart.
PHARMACOLOGY
Trazodone differs significantly from other known psychopharmacological agents in pharmacological profile.
Trazodone impedes the uptake of serotonin by the membrane. The depletion of brain serotonin by fenfluramine is impeded with small doses of the drug, but doses of 50 mg/kg do not affect the concentration of serotonin in the rat brain.
Trazodone is a weak inhibitor of noradrenaline re-uptake in experimental studies but is practically inactive against I-dopa, histamine and acetylcholine. It is not known to inhibit monoamine oxidase.
Trazodone exhibits CNS depressant activities, with motor activity being decreased in cats, rats and mice, and hexobarbital-induced sleeping time being increased in mice. At doses which do not influence the unconditioned response (ED50 = 19.5 mg/kg p.o.) trazodone also inhibits conditioned avoidance responding in rats. Trazodone has very weak muscle relaxant activity, but anticonvulsant, anti-antireserpine or cataleptogenic effects.
In mice doses at which motor activity is unaffected (10 mg/kg p.o.) suppress responses to painful stimuli, and 12.5 mg/kg i.p significantly inhibits oxotremorine-, clonidine- and nicotine-induced tremors. Trazodone does not inhibit the stereotyped behaviour due to amphetamine or apomorphine, but does protect grouped mice against amphetamine-induced toxicity.
The infusion of trazodone in rats produces first a fall in mean blood pressure, followed by ECG changes only as a consequence of the hypotension produced. There was no effect on His bundle conduction nor evidence of heart block or rhythm disturbance other than the slowing of normal sinus rhythm when anesthetized dogs were administered graded doses of trazodone between 1 and 30 mg/kg i.v. Doses of 0.5 to 5 mg/kg imipramine, however, slowed impulse conduction as well as atrial transmission. Similar doses of trazodone and imipramine had comparable effects on the sleep-wakefulness cycle in rats; REM sleep was reduced with 10 mg/kg p.o. and completely suppressed with 160 mg/kg.
TOXICOLOGY
Acute Toxicity:
LD50 in mg/kg (95% confidence limits) Species | ||||||||||||
| Route | Mouse | Rat | Rabbit | Dog | ||||||||
| intravenous | 91 (82-101) | 91 (86-96) | 52 | 40 | ||||||||
| intraperitoneal | 210 (189-233) | 178 (162-196) | - | - | ||||||||
| oral | 610 (540-689) | 690 (616-733) | 560 | 500 | ||||||||
Signs of toxicity included dyspnea, salivation, ptosis, aggressivity, hypoactivity, prostration and clonic convulsions.
Subacute and Chronic Toxicity:
Several subacute studies were conducted in rats, using doses ranging from 100 to 450 mg/kg/day p.o. for one to four months. The main toxic effects observed were decreased body weight gain and slight liver enlargement in males. There were some deaths at the highest dose. Tremors, vomiting and clonic convulsions were produced in dogs given 50 and 100 mg/kg/day p.o. for one month.
Of two dogs receiving 100 mg/kg, one died after 3 weeks. Administration of approximately 250 mg/kg/day in the diet of rats for six months resulted in significantly greater liver weights than in control rats and slightly lower weight gain in males. No toxic effects were evident in dogs receiving 5 and 25 mg/kg/day for 6 months.
Rats were given doses of 0, 30, 100 and 300 mg/kg/day p.o for 18 months. All treated groups demonstrated decreased body weight gain, and males in the highest dose group showed significantly reduced food intake. Rats at the 100 mg/kg dose exhibited some lethargy and salivation immediately following dosing, but at the lowest dose level, no behavioral or pathologic effects were observed. There was excessive salivation and the animals became inactive, assuming a prone position for approximately 3 hours after dosing with the highest dose. There were occasional body tremors also. Within 30 weeks, tolerance developed to all these reactions.
Oral doses of 0, 10, 20 and 40 mg/kg/day were given to beagle for one year. Following the death of 3/10 animals in the highest dose group, the dose was reduced to 30 mg/kg/day after 8 weeks. There were no abnormal signs at the 10 mg/kg level. One animal in the 20 mg/kg group was found prostate and panting on one occasion and another was unexpectantly found dead near the end of the study. Occasional transient ataxia, excessive salivation and convulsions were produced with 40 mg/kg. Upon reducing the dosage to 30 mg/kg following the three deaths, a fourth death occurred 16 weeks later, subsequent to convulsions. During the final 6 months of the study, a fifth animal became hypersensitive to touch and aggressive.
Apart from one case of transient anemia in the 20 mg/kg group and slightly elevated SGPT values in 2 of the high dose dogs during the final 3 months, hematological and biochemical analyses were normal.
Trazodone was administered in doses of 0, 20, 40 and 80 mg/kg/day by gavage for one year to groups of 6 rhesus monkeys. A slight, dose-related decrease in activity and tremors in 3 high dose monkeys were the only effects noted. Both of these effects decreased during the study.
Reproductive Studies: Fertility and general reproductive performance of male and female rats were unaffected by doses of up to 250 mg/kg/day. The birth weight of pups was significantly reduced at 300 mg/kg. Two rat studies were conducted: one in which rats were given 100 and 210 mg/kg/day p.o. during days 10 to 15 and 6 to 15 of gestation, respectively; and another in which doses of 150 to 450 mg/kg/day p.o. were given during days 9 to 14 of gestation. Only a sedative effect on dams was noted at 100 mg/kg. Increased sedation decreased maternal and fetal weights and retarded ossification were produced at doses of 150 mg/kg and higher. A significant increase in resorptions and stillborn fetuses, in addition to retarded fetal growth, occurred with 300 and 450 mg/kg. Isolated cases of branched rib, separated thoracic arch, umbilical hernia and exencephalia were also noted.
The only peri- and post-natal effects of up to 300 mg/kg/day of trazodone in rats were reduced birth and weaning weights of offspring in the highest dosage group.
Carcinogenicity Studies:
Rats were used to conduct a two year carcinogenicity study at doses of 0, 40 and 80 mg/kg/day. In both treatment groups, larger numbers of female rats died sooner than controls; most deaths were related to the presence of pituitary tumors.
In both treatment groups at 12, 13 and 14 months, the incidence of palpable masses (mammary tumours, cysts, etc.) was increased also. These observations may be related to trazodone's effects on prolactin secretion. (Acute administration caused an increase in prolactin blood levels whereas chronic administration did not. Turnover, however, was not studied. When a neuroleptic was used as a positive control, similar results were produced.) The relative incidences of male rats with pituitary tumours were reversed. These results may have been influenced by the early deaths due to nephritis and other causes, however.
BIBLIOGRAPHY
- 1. Baiocchi L, Frigerio A, Giannangeli M, Palazzo G. Basic metabolites of trazodone in humans. Arzneim-Forsch 1974; 24: 1699-1706.
- 2. Ban TA, Lehmann HE, Amin M, et al. Comprehensive clinical studies with trazodone. Curr Ther Res 1973; 15:540-51.
- 3. Barcelona PS. Investigations on the possible teratogenic effects of trazodone in rats and rabbits. Boll Chim Farm 1970; 109:323-32.
- 4. Bardin ED, Krieger JN. Pharmacological priapism: Comparison of trazodone- and papaverine associated cases. Int Urol Nephrol 1990; 22: 147-52.
- 5. Bayer AJ, Pathy MSJ, Cameron A, et al. A comparative study of conventional and controlled-release formulations of trazodone in elderly depressed patients. Clin Neuropharmacol 1989; 12 (Suppl. 1):S50-5.
- 6. Benkelfat C, Gay C, Renardet M. Use of interactive computer technology in open clinical trials. Study with trazodone in depressed patients. Neuropsychobiology 1986; 15 (Suppl. 1): 10--4.
- 7. Brogden RN, Heel RC, Speight TM, Avery GS. Trazodone: A review of its pharmacological properties and therapeutic use in depression and anxiety. Drugs 1981; 21:401-29.
- 8. Cole JO, Schatzberg AF, Sniffin C, et al. Trazodone in treatment resistant depression: An open study. J Clin Psychopharmacol 1981; 1 (SUPPI. 6):49S-54s.
- 9. Debbas NMG, Ankier SI, Warrington SJ. Trazodone conventional and controlled-release formulations: Pharmacodynamic effects after single and repeated administration. Curr Med Res Opin 1989; 11:501-9.
- 10. Feighner JP. Trazodone, a triazolopyridine derivative in primary depressive disorder. J Clin Psychiatry 1980; 41: 250-255.
- 11. Fernstrom JD, Van Itallie CM, Fernstrom MH. Effects of acute and chronic trazodone administration on serum prolactin levels in adult female rats. Life Sci 1983; 33:2559-65.
- 12. Gamble DE, Peterson LG. Trazodone overdose: Four years of experience from voluntary reports. J Clin Psychiatry 1986; 47:544-6.
- 13. Garattini S, De Gaetano G, Samanin R, et al. Effects of trazodone on serotonin in the brain and platelets of the rat. Biochem Pharmacol n1976; 25~13-6.
- 14. Gomoll AW, Byrne JE. Trazodone and imipramine: Comparative effects on canine cardiac conduction. Eur J Pharmacol 1979; 57:335-42.
- 15. Harcus AW, Ward AE, Ankier SI, Kimber GR. A comparative bioavailability study of molipaxin capsules and a trazodone liquid formulation in normal volunteers. J Clin Hosp Pharm 1983; 8:125- 32.
- 16. Hell K, Wernze H. Drug-induced changes in prolactin secretion. Clinical implications. Med Taxicol 1988; 3:463-98. Janowsky D, Curtis G, Zisook S, et al. Ventricular arrhythmias possibly aggravated by trazodone. Am J Psychiatry 1983; 140:796- 7
- 17. Jones SD. Ejaculatory inhibition with trazodone. J Clin Psychopharmacol 1984; 4:279-81.
- 18. Kraft TB. Psychosis following trazodone administration. Am J Psychiatry 1983; 140: 1383-4.
- 19. Krogh CME, Gillis MC, Bisson R, et a1 (eds). Compendium of pharmaceuticals and specialties 24th edition, Toronto, Canadian Pharmaceutical Association, 1985; 299-300.
- 20. Lefkowitz D, Kilgo G, Lee S. Seizures and trazodone therapy. Arch Gen Psychiatry 1985; 42:523.
- 21. Lesar T, Kingston R, Dahms R, Saxena K. Trazodone overdose. Ann Emerg Med 1983; 12:221-3.
- 22. Lippmann S, Bedford P, Manshadi M, Mather S. Trazodone cardiotoxicity. Am J Psychiatry 1983;140:1383.
- 23. Lisciani R, Campana A, Barcellona PS. Comparative cardiovascular toxicity of trazodone and imipramine in the rat. Arch Toxic01 1978; SUPPI. 1 :169-72.
- 24. Munday B, Kendall MJ, Mitchard M. A single dose study of trazodone with an assessment of its effect on mood and arousal. Br J Clin Pharmacol 1975; 2:19-24.
- 25. Newton R. The side effect profile of trazodone in comparison to an active control and placebo. J Clin Psychopharmacol 1981; 1 (Suppl. 6):89S-93s.
- 26. Rake1 RE. The greater safety of trazodone over tricyclic antidepressant agents: 5-year experience in the United States. Psychopathology 1987; 20 (Suppl. 1):57-63.
- 27. Rawls N. Trazodone. Drug Intell Clin Pharm 1982; 16:7-13.
- 28. Rivett KF, Barcellona PS. Toxicology of trazodone. Trazodone. Mod Probl Pharmacopsychiat 1974; 9:76-86.
- 29. Sacks M, Miller F, Gunn J, et al. Unusual erectile activity as a side effect of trazodone. Hosp Community Psychiatry '1985; 36:298.
- 30. Silvestrini B, Cioli V, Burberi S, Catanese B. Pharmacological properties of AF 1161 , a new psychotropic drug. Int J Neuropharmacol1968; 7: 587-599.
- 31. Silvestrini B, Lisciani R. Pharmacology of trazodone. Curr Ther Res 1973; 15 (Suppl. 10):749-53.
- 32. Silvestrini B, Vaieri P. Trazodone, a new avenue in the treatment of depression. Psychopathology 1984; 17 (Suppl. 2):3-14.
- 33. 33. Suzuki Y. Teratogenicity and placental transfer of trazodone. Trazodone. Mod Probl Pharmacopsychiat 1974; 9:87-94. Van De Merwe TJ, Silverstone T, Ankier SI, et al. A double--blind, non-crossover placebo-controlled study between group comparison of trazodone and amitriptyline on cardiovascular function in major depressive disorder. Psychopathology 1984; 17 (Suppl. 2):64-76.
- 34. Warrington SJ, Ankier SI, Turner P. An evaluation of possible interactions between ethanol and trazodone or amitriptyline. Br J Clin Pharmacol 1984: 18:549-57.
- 35. Yamatsu K, Kaneko T, Yamanishi Y, et al. A possible mechanism of central action of trazodone in rats. Trazodone. Mod Probl Pharmacopsychiat 1974; 9:11-7.
- 36. Physician's Desk Reference 43rd edition, Edward R. Barnhurst (pub.), 1989; 1264-6.
- 37. Psychotherapeutic agents. Antidepressants. Trazodone hydrochloride. In: McEvoy GK, Litvak K, Mendham NA, et al (eds.). AHFS Drug Information 89, Bethesda, American Society of Hospital Pharmacists, 1989;1124-8.
- 38. A two-way, single-dose bioavailability study of trazodone HCI 150 mg tablets in normal healthy male volunteers. September 1991.
- 39. CPS. Ottawa (ON): Canadian Pharmacist Association; c2015 Accessed Date: November 16, 2015. Trazodone General Monograph. Available from: http://e-therapeutics.ca. Also available in paper copy from the publisher.
- 40. Product Monograph for WELLBUTRIN® SR 150 mg Sustained-Release Tablets. Valeant Canada LT. Laval, Canada. Revised: September 10, 2013.
- 41. Product Monograph for Desyrel 50 and 100 mg Tablets, manufactured by Bristol-Myers Squibb Canada, dated October 29, 2004 (Control # 094864).
- 42. Product Monograph for TEVA-TRAZODONE 50 mg, 100 mg and 150 mg Tablets, manufactured by Teva Canada Ltd., dated February 5, 2016 (Control # 187466).