


Product Monograph - Taro-Bupropion XL
RECENT MAJOR LABEL CHANGES
| 4.1 Dosing Considerations | 03/2025 |
|---|---|
| 7 WARNINGS AND PRECAUTIONS, Cardiovascular | 03/2025 |
TABLE OF CONTENTS
Sections or subsections that are not applicable at the time of authorization are not listed.
RECENT MAJOR LABEL CHANGES ............................................................................................ 2
TABLE OF CONTENTS .............................................................................................................. 2
PART I: HEALTH PROFESSIONAL INFORMATION ..................................................................... 4
1 INDICATIONS ....................................................................................................................... 4
1.1 Pediatrics ........................................................................................................................... 4
1.2 Geriatrics ........................................................................................................................... 4
2 CONTRAINDICATIONS .......................................................................................................... 4
3 SERIOUS WARNINGS AND PRECAUTIONS BOX ..................................................................... 5
4 DOSAGE AND ADMINISTRATION ......................................................................................... 5
4.1 Dosing Considerations ....................................................................................................... 5
4.2 Recommended Dose and Dosage Adjustment ................................................................... 5
4.4 Administration ................................................................................................................... 7
4.5 Missed Dose ...................................................................................................................... 7
5 OVERDOSAGE ...................................................................................................................... 7
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING ......................................... 9
7 WARNINGS AND PRECAUTIONS ......................................................................................... 10
7.1 Special Populations .......................................................................................................... 16
7.1.1 Pregnant Women .......................................................................................................... 16
7.1.2 Breast-feeding .............................................................................................................. 16
7.1.3 Pediatrics ...................................................................................................................... 16
7.1.4 Geriatrics ...................................................................................................................... 16
8 ADVERSE REACTIONS ......................................................................................................... 17
8.1 Adverse Reaction Overview ............................................................................................. 17
8.2 Clinical Trial Adverse Reactions ....................................................................................... 18
8.3 Less Common Clinical Trial Adverse Reactions ................................................................ 24
8.5 Post-Market Adverse Reactions ....................................................................................... 28
9 DRUG INTERACTIONS ........................................................................................................ 29
9.1 Serious Drug Interactions ................................................................................................ 29
9.2 Drug Interactions Overview ............................................................................................. 29
9.3 Drug-Behavioural Interactions ......................................................................................... 30
9.4 Drug-Drug Interactions .................................................................................................... 30
9.5 Drug-Food Interactions .................................................................................................... 34
9.6 Drug-Herb Interactions .................................................................................................... 34
9.7 Drug- Laboratory Test Interactions .................................................................................. 34
10 CLINICAL PHARMACOLOGY .............................................................................................. 34
10.1 Mechanism of Action .................................................................................................... 34
10.2 Pharmacodynamics ........................................................................................................ 35
10.3 Pharmacokinetics .......................................................................................................... 35
11 STORAGE, STABILITY AND DISPOSAL................................................................................ 39
12 SPECIAL HANDLING INSTRUCTIONS ................................................................................ 39
PART II: SCIENTIFIC INFORMATION ....................................................................................... 41
13 PHARMACEUTICAL INFORMATION .................................................................................. 41
14 CLINICAL TRIALS .............................................................................................................. 41
14.1 Clinical Trials by Indication ............................................................................................ 41
Major Depressive Disorder .................................................................................................... 41
Prevention of Seasonal Major Depressive Episodes .............................................................. 43
14.3 Comparative Bioavailability Studies ............................................................................... 44
15 MICROBIOLOGY .............................................................................................................. 48
16 NON-CLINICAL TOXICOLOGY ............................................................................................ 50
17 SUPPORTING PRODUCT MONOGRAPHS .......................................................................... 51
PATIENT MEDICATION INFORMATION ................................................................................. 52
PART I: HEALTH PROFESSIONAL INFORMATION
1 INDICATIONS
TARO-BUPROPION XL is indicated for:
- the symptomatic relief of major depressive illness
- the prevention of major depressive illness with an autumn-winter seasonal pattern.
The effectiveness of Bupropion Hydrochloride Extended-Release Tablets in long-term use (greater than 8 weeks) has not been evaluated in controlled trials for major depressive illness. The duration of treatment for the prevention of seasonal major depressive episodes lasted 4 - 6 months.
1.1 Pediatrics
Pediatrics (<18 years of age): Based on the data submitted and reviewed by Health Canada, the safety and efficacy of Bupropion Hydrochloride Extended-Release Tablets in pediatric patients have not been established; therefore, Health Canada has not authorized an indication for pediatric use (see Potential association with behavioural and emotional changes, including self-harm).
1.2 Geriatrics
Geriatrics (≥65 years of age): No overall differences in safety or effectiveness were observed between these subjects and younger subjects, but because elderly patients are more likely to have decreased renal function, greater sensitivity of some older individuals to bupropion cannot be ruled out (see Renal Impairment and 4. DOSAGE AND ADMINISTRATION).
2 CONTRAINDICATIONS
TARO-BUPROPION XL is contraindicated in patients:
- receiving other medications that contain bupropion hydrochloride such as bupropion hydrochloride sustained-release tablets, Zyban®, and Contrave®, because the incidence of seizure is dose dependent (see Seizures).
- with a current seizure disorder or history of seizures (see Seizures).
- with a current or prior diagnosis of bulimia or anorexia nervosa because of a higher incidence of seizures (see Seizures) noted in patients treated for bulimia with the immediate release formulation of bupropion.
- undergoing abrupt withdrawal from alcohol or benzodiazepines or other sedatives.
- taking concurrent monoamine oxidase inhibitors (MAOIs) (see 9.4 Drug-Drug Interactions). Allow 14 days between discontinuation of one drug and the start of another.
taking concurrent thioridazine, since bupropion may inhibit thioridazine metabolism, thus causing an increase in thioridazine levels and a potential increased risk of thioridazine-related serious ventricular arrhythmias and sudden death (see 9.4 Drug-Drug Interactions). Allow 14 days between discontinuation of one drug and the start of
- with known hypersensitivity to bupropion or to any of the non-medicinal components of the formulation. For a complete listing of excipients, see 6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING.
3 SERIOUS WARNINGS AND PRECAUTIONS BOX
Serious Warnings and Precautions
| Increased risk of self-harm, harm to others, suicidal thinking and behavior with antidepressants use. Closely monitor all antidepressant-treated patients for clinical worsening and for emergence of agitation-type and/or suicidal thoughts and behaviors (see Potential association with behavioural and emotional changes, including self-harm). |
|---|
4 DOSAGE AND ADMINISTRATION
4.1 Dosing Considerations
TARO-BUPROPION XL (bupropion hydrochloride) is not indicated for use in children under 18 years of age (see Potential association with behavioural and emotional changes, including self-harm).
Unmasking of Brugada syndrome has been reported with bupropion. It is advised to avoid use of TARO-BUPROPION XL in patients with Brugada syndrome. If treatment with TARO-BUPROPION XL is considered in patients with Brugada syndrome and patients at risk of having Brugada syndrome (e.g., patients with unexplained syncope, patients with a family history of cardiac arrest or sudden death), an evaluation by a cardiologist should be sought prior to initiating treatment, to assess suitability of treatment and to determine the most appropriate strategy for monitoring cardiac effects (see Unmasking of Brugada syndrome).
When switching patients from bupropion hydrochloride sustained-release tablets to TARO-BUPROPION XL, give the same total daily dose when possible (for example 150 mg bupropion hydrochloride sustained-release tablets twice a day may be switched to 300 mg TARO-BUPROPION XL once daily). TARO-BUPROPION XL should never be taken concurrently with bupropion hydrochloride sustained-release tablets, bupropion hydrochloride extended-release tablets or other medications containing bupropion.
4.2 Recommended Dose and Dosage Adjustment
Recommended Dose
- Major Depressive Disorder
Dosing with TARO-BUPROPION XL Tablets should begin at 150 mg/day given as a single daily dose in the morning.
The dose of TARO-BUPROPION XL may be increased to the 300 mg/day maximum dose as early as 1 week after initiation of treatment. The usual adult target dose for TARO-BUPROPION XL
Tablets is 300 mg/day, given once daily in the morning.
- Prevention of Seasonal Major Depressive Episodes
TARO-BUPROPION XL should be initiated in the autumn prior to the onset of depressive symptoms. Treatment should continue through the winter season and should be tapered and discontinued in early spring. The timing of initiation and duration of treatment should be individualized based on the patient's historical pattern of seasonal major depressive episodes. Patients whose seasonal depressive episodes are infrequent or not associated with significant impairment should generally not be treated prophylactically.
Dosing with TARO-BUPROPION XL Tablets should begin at 150 mg/day given as a single daily dose in the morning. The dose of TARO-BUPROPION XL may be increased to the 300mg/day maximum dose after 1 week. The usual adult target dose for TARO-BUPROPION XL Tablets is 300 mg/day, given once daily in the morning.
Doses of bupropion hydrochloride extended-release tablets above 300 mg/day have not been studied for the prevention of seasonal major depressive episodes.
Dosage Adjustment
- Major Depressive Disorder
The dose can be reduced to or maintained at 150 mg daily if the patient is unable to tolerate the 300 mg/day dose.
- Prevention of Seasonal Major Depressive Episodes
The dose can be reduced to or maintained at 150 mg daily if the patient is unable to tolerate the 300 mg/day dose. For patients taking 300 mg/day during the autumn-winter season, the dose should be tapered to 150 mg/day for 2 weeks prior to discontinuation.
Hepatic Impairment
Mild and Moderate Hepatic Impairment: Given the variable pharmacokinetics of bupropion in patients with either mild or moderate hepatic impairment (Child-Pugh Grade A or B), treatment with TARO-BUPROPION XL should be initiated at the lowest recommended dose. Maintenance dose may be adjusted according to clinical response and tolerance. Caution should be exercised as there is no clinical experience with bupropion hydrochloride extended-release tablets in hepatically impaired patients (see also Hepatic/Biliary/Pancreatic).
Severe Hepatic Impairment: Given the risks associated with both peak bupropion levels and drug accumulation, TARO-BUPROPION XL is not recommended for use in patients with severe hepatic impairment. However, should clinical judgement deem it necessary, the drug should be used only with extreme caution (see also Hepatic/Biliary/Pancreatic). The dose should not exceed 150 mg every day or every other day in these patients. Any theoretical dose reduction for this patient population based on the findings of the pharmacokinetic studies may result in toxic drug levels in these patients (see Hepatic Insufficiency and Hepatic/Biliary/Pancreatic).
- Renal Impairment
TARO-BUPROPION XL should be used with caution in patients with renal impairment due to the potential for drug accumulation, and a reduced frequency and/or dose should be considered (see Renal).
All patients with hepatic or renal impairment should be closely monitored for possible adverse effects (e.g., insomnia, dry mouth, seizures) that could indicate high drug or metabolite levels.
- Treatment of Pregnant Women During the Third Trimester
Post-marketing reports indicate that some neonates exposed to bupropion hydrochloride sustained-release tablets, SSRIs (Selective Serotonin Reuptake Inhibitors), or other newer anti-depressants late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding (see 7.1.1 Pregnant Women). When treating pregnant women with TARO-BUPROPION XL during the third trimester, the physician should carefully consider the potential risks and benefits of treatment. The physician may consider tapering TARO-BUPROPION XL in the third trimester.
- Geriatrics or Debilitated Patients
No pharmacokinetic or therapeutic trials have been conducted to systematically investigate dose requirements in patients who are elderly or debilitated (see 7.1.4 Geriatrics). As such patients may have reduced clearance of bupropion and its metabolites, and/or increased sensitivity to the side-effects of CNS active drugs, treatment with TARO-BUPROPION XL should be initiated at the lowest recommended dose (150 mg/day).
- Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of bupropion hydrochloride extended-release tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see Potential association with behavioural and emotional changes, including self-harm and 7.1.3 Pediatrics).
4.4 Administration
Patients should be advised to swallow TARO-BUPROPION XL tablets whole with fluids, and NOT to chew, divide, crush or otherwise tamper with the tablets in any way that might affect the release rate of bupropion (see Misuse of TARO-BUPROPION XL by injection or inhalation ). The inhalation of crushed tablets or injection of dissolved bupropion may lead to a rapid release, faster absorption and a potential overdose. Seizures and/or cases of death have been reported when bupropion has been administered intra-nasally or by parenteral injection (see Seizures).
4.5 Missed Dose
TARO-BUPROPION XL should be taken at the same time each day and no more than one dose should be taken each day. If the normal administration time has been missed, the dose should be skipped, and administration resumed at the normal administration time of the following day.
5 OVERDOSAGE
In addition to those events reported under 8 ADVERSE REACTIONS, overdose has resulted in symptoms including drowsiness, loss of consciousness, status epilepticus, and ECG changes such as conduction disturbances (including QRS prolongation) or arrhythmias; cases of fatal outcome have been reported. QTc prolongation has also been reported but was generally seen in conjunction with QRS prolongation and increased heart rate. No overdoses occurred during bupropion hydrochloride extended-release tablets clinical trials. Three overdoses with bupropion hydrochloride sustained-release tablets occurred during clinical trials. One patient ingested 3000 mg of bupropion hydrochloride sustained-release tablets and vomited quickly after the overdose; the patient experienced blurred vision and light-headedness. A second patient ingested a “handful” of bupropion hydrochloride sustained-release tablets and experienced confusion, lethargy, nausea, jitteriness, and seizure. A third patient ingested 3,600 mg of bupropion hydrochloride sustained-release tablets and a bottle of wine; the patient experienced nausea, visual hallucinations, and “grogginess”. None of the patients experienced further sequelae.
The information included in the remainder of this section is based on the clinical experience with overdosage of the immediate release formulation of bupropion. Thirteen overdoses occurred during clinical trials. Twelve patients ingested 850 to 4200 mg and recovered without significant sequelae. Another patient who ingested 9000 mg of Bupropion Hydrochloride Tablets and 300 mg of tranylcypromine experienced a grand mal seizure and recovered without further sequelae.
Since introduction, overdoses of up to 17,500 mg of the immediate release formulation of bupropion hydrochloride tablets, and up to 10,500 mg of bupropion hydrochloride extended-release tablets have been reported. Seizure was reported in approximately one-third of all cases. Other serious reactions reported with overdoses of bupropion hydrochloride tablets or bupropion hydrochloride extended-release tablets alone included hallucinations, loss of consciousness, respiratory arrest, amnesia, and sinus tachycardia. Fever, muscle rigidity, rhabdomyolysis, hypotension, stupor, coma, respiratory failure, delirium, and cerebral edema have been reported when bupropion hydrochloride tablets or bupropion hydrochloride extended-release tablets was part of multiple drug overdoses.
Although most patients recovered without sequelae, deaths associated with overdoses of bupropion hydrochloride tablets alone have been reported rarely in patients ingesting large doses of bupropion hydrochloride tablets. Multiple uncontrolled seizures, bradycardia, cardiac failure, and cardiac arrest prior to death were reported in these patients.
Serotonin toxicity, also known as serotonin syndrome, is a potentially life-threatening condition and has been reported with bupropion in association with overdose. These cases include chronic administration at supratherapeutic doses (doses just above the maximum recommended daily dose, e.g. 600-800 mg). Symptoms of serotonin toxicity possibly include hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, mental status changes including confusion, irritability, extreme agitation progressing to delirium and coma and supportive symptomatic treatment should be initiated. If concomitant treatment with TARO-BUPROPION XL or serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). If serotonin toxicity is suspected, discontinuation of TARO-BUPROPION XL should be considered (see Serotonin Toxicity / Serotonin Syndrome).
Management of Overdose
In the event of overdose, hospitalization is advised. Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm (ECG) and vital signs. EEG monitoring is also recommended for the first 48 hours post-ingestion. General supportive and symptomatic measures are also recommended. Induction of emesis is not recommended. Gastric lavage with a large bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion or in symptomatic patients.
Activated charcoal should be administered. There is no experience with the use of forced diuresis, dialysis, hemoperfusion, or exchange transfusion in the management of bupropion overdoses. No specific antidotes for bupropion are known.
Due to the dose-related risk of seizures with bupropion hydrochloride extended-release tablets, hospitalization following suspected overdose should be considered. Based on studies in animals, it is recommended that seizures be treated with intravenous benzodiazepine administration and other supportive measures, as appropriate.
In managing overdosage, consider the possibility of multiple drug involvement. The physician should consider contacting a poison control centre for additional information on the treatment of any overdose. Telephone numbers for certified poison control centres are listed in the Compendium of Pharmaceuticals and Specialties (CPS).
| For the most recent information in the management of a suspected drug overdose, contact your regional poison control centre or Health Canada’s toll-free number, 1-844 POISON-X (1-844-764-7669). |
|---|
6 DOSAGE FORMS, STRENGTHS, COMPOSITION AND PACKAGING
Table 1: Dosage Forms, Strengths, Composition and Packaging
| Route of Administration | Dosage Form/Strength /Composition | Non-medicinal Ingredients |
| Oral | Tablets: 150 mg and 300 mg | Ethylcellulose, glyceryl behenate, hydroxypropyl cellulose, hypromellose, iron oxide black, lactose monohydrate, methylacrylic acid- copolymer dispersion, polyethylene glycol, povidone, propylene glycol, shellac glaze, silicon dioxide, stearic acid, and triethyl citrate |
TARO-BUPROPION XL 150 mg tablets are supplied as white to pale yellow, round, film-coated tablets imprinted with ‘L2’ in black ink on one side and plain on the other side.
TARO-BUPROPION XL 300 mg tablets are supplied as white to pale yellow, round, film-coated tablets imprinted with ‘L’ in black ink on one side and plain on the other side.
TARO-BUPROPION XL 150 mg tablets are supplied in bottles of 90 and 500 tablets.
TARO-BUPROPION XL 300 mg tablets are supplied in bottles of 90 and 500 tablets.
7 WARNINGS AND PRECAUTIONS
General
- Misuse of TARO-BUPROPION XL by injection or inhalation
TARO-BUPROPION XL is intended for oral use only. The inhalation of crushed tablets or injection of dissolved bupropion has been reported, and may lead to a rapid release, faster absorption and a potential overdose. Seizures and/or cases of death have been reported when bupropion has been administered intra-nasally or by parenteral injection (see 4.4 Administration).
Cardiovascular
- Unmasking of Brugada syndrome
There have been isolated post-marketing reports of unmasking of Brugada syndrome with bupropion. Brugada syndrome is a disorder characterized by syncope, characteristic ECG changes, such as right bundle branch block and ST segment elevation in right precordial leads, and a risk of cardiac arrest and sudden death.
It is advised to avoid use of TARO-BUPROPION XL in patients with Brugada syndrome. If TARO-BUPROPION XL is considered in patients with Brugada syndrome or in patients at risk of having Brugada syndrome (e.g., patients with unexplained syncope, patients with a family history of cardiac arrest or sudden death), an evaluation by a cardiologist should be sought prior to initiating treatment, to assess suitability of treatment and to determine the most appropriate strategy for monitoring cardiac effects. Patients should be informed about the signs and symptoms of Brugada syndrome. If unmasking of Brugada syndrome occurs, discontinue treatment with TARO-BUPROPION XL.
- Hypertension
In clinical practice, hypertension, in some cases severe, requiring acute treatment, has been reported in patients receiving bupropion alone and in combination with nicotine replacement therapy. These events have been observed in both patients with and without evidence of pre-existing hypertension.
Data from a comparative study of the sustained-release formulation of bupropion (Zyban® Sustained-Release Tablets), nicotine transdermal system (NTS), the combination of sustained-release bupropion plus NTS, and placebo as an aid to smoking cessation suggest a higher incidence of treatment-emergent hypertension in patients treated with the combination of sustained-release bupropion and NTS. In this study, 6.1% of patients treated with the combination of sustained- release bupropion and NTS had treatment-emergent hypertension compared to 2.5%, 1.6%, and 3.1% of patients treated with sustained-release bupropion, NTS, and placebo, respectively. The majority of these patients had evidence of pre-existing hypertension. Three patients (1.2%) treated with the combination of Zyban® and NTS and one patient (0.4%) treated with NTS had study medication discontinued due to hypertension compared to none of the patients treated with Zyban® or placebo. Monitoring of blood pressure is recommended in patients who receive the combination of bupropion and nicotine replacement.
There is limited clinical experience establishing the safety of bupropion in patients with a recent history of myocardial infarction or unstable heart disease. Therefore, care should be exercised if it is used in these groups. In a study of depressed inpatients with stable heart failure, bupropion was associated with a rise in supine blood pressure, resulting in discontinuation of two patients for exacerbation of baseline hypertension.
Driving and Operating Machinery
Any psychoactive drug may impair judgement, thinking or motor skills. Therefore, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that the drug treatment does not affect their performance adversely.
Endocrine and Metabolism
- Decreased Appetite and Weight
In clinical trials bupropion hydrochloride sustained-release tablets were associated with dose-related weight loss. In eight-week, controlled trials mean weight loss for trial completers was 0.1 kg for placebo, 0.8 kg for bupropion hydrochloride sustained-release tablets 100 mg/day, 1.4 kg at 150 mg/ day, and 2.3 kg at 300 mg/day.
In 3 placebo-controlled clinical trials of seasonal depression using bupropion hydrochloride extended-release tablets (up to 6 months of treatment), 23% of subjects who received bupropion hydrochloride extended-release tablets lost >5lbs, compared to 11% of subjects who received placebo. The mean weight change from baseline to the subject's last visit was
-0.9 kg in the bupropion hydrochloride extended-release tablets group and 0.8kg in the placebo group.
If weight loss is a major presenting sign of a patient’s depressive illness, the potential anorectic and/or weight reducing effect of bupropion hydrochloride should be considered.
- Drugs Metabolized by Cytochrome P450 (CYP2D6)
Drugs which require metabolic activation by CYP2D6 in order to be effective (e.g. tamoxifen), may have reduced efficacy when administered concomitantly with inhibitors of CYP2D6 such as bupropion. Therefore, bupropion should not be used in combination with tamoxifen and other treatment options should be considered. (see 9.4 Drug-Drug Interactions).
Hepatic/Biliary/Pancreatic
- Hepatic Impairment
The results of two single dose pharmacokinetic studies indicate that the clearance of bupropion is reduced in all subjects with Child-Pugh Grades C hepatic impairment, and in some subjects with milder forms of liver impairment. Given the risks associated with both peak bupropion levels and drug accumulation, TARO-BUPROPION XL is not recommended for use in patients with severe hepatic impairment. However, should clinical judgement deem it necessary, it should be used only with extreme caution at a reduced dose, to a maximum dose of 150 mg every other day.
All patients with hepatic impairment should be closely monitored for possible adverse effects (e.g., insomnia, dry mouth, seizures) that could indicate high drug or metabolite levels (see 4.1 Dosing Considerations, and Hepatic Insufficiency).
- Potential for Hepatotoxicity
In rats receiving large doses of bupropion chronically, there was an increase in incidence of hepatic hyperplastic nodules and hepatocellular hypertrophy. In dogs receiving large doses of bupropion chronically, various histologic changes were seen in the liver, and laboratory tests suggesting mild hepatocellular injury were noted.
Immune
- Anaphylactic reaction
Anaphylactoid/anaphylactic reactions characterized by symptoms such as pruritus, urticaria, angioedema, and dyspnea requiring medical treatment have been reported in clinical trials with bupropion at a rate of 1-3 per thousand. In addition, there have been rare spontaneous postmarketing reports of erythema multiforme, Stevens-Johnson syndrome, and anaphylactic shock associated with bupropion. In uncontrolled and controlled clinical trials, skin disorders, primarily rashes, pruritis, and urticaria, lead to discontinuation of 1.5% and 1.9 %, respectively of bupropion-treated subjects. A patient should stop taking TARO-BUPROPION XL and consult a doctor if experiencing allergic or anaphylactoid/anaphylactic reactions (e.g., skin rash, pruritus, hives, chest pain, edema, and shortness of breath) during treatment.
- Cutaneous lupus erythematosus (CLE)/Systemic lupus erythematosus (SLE):
Treatment with bupropion hydrochloride extended-release tablets has been associated with the development of cutaneous lupus erythematosus which has resolved following withdrawal of medication. Exacerbation of systemic lupus erythematosus has also occurred. Symptoms such as arthralgia, myalgia, rash, swelling and positive autoantibodies have been observed. If any of the above effects should occur after TARO-BUPROPION XL treatment, TARO-BUPROPION XL should be discontinued and the patient should be carefully evaluated for appropriate clinical management.
Hypersensitivity
Arthralgia, myalgia and fever have also been reported in association with rash and other symptoms suggestive of delayed hypersensitivity. These symptoms may resemble serum sickness.
Bupropion should be discontinued immediately if any hypersensitivity reactions are experienced. Symptoms of hypersensitivity should be treated in accordance with established medical practice. Clinicians should be aware that symptoms may persist beyond the discontinuation of bupropion, and clinical management should be provided accordingly. In post-market experience, there have been reports of hypersensitivity reactions in patients who consumed alcohol while taking bupropion. As the contribution of alcohol to these reactions has been established, patients should avoid alcohol when they are taking bupropion (see 9.3 Drug-Behavioural Interactions).
Neurologic
- Seizures
Patients should be made aware that TARO-BUPROPION XL contains the same active ingredient (bupropion hydrochloride) as Zyban® and bupropion hydrochloride sustained-release tablets. TARO-BUPROPION XL should NOT be administered to patients already receiving a product containing bupropion hydrochloride (see 2 CONTRAINDICATIONS).
The recommended dose of extended release bupropion tablets should not be exceeded since bupropion is associated with a dose-related risk of seizure. The overall incidence of seizure with bupropion hydrochloride extended-release tablets in clinical trials at doses up to 450 mg/day was approximately 0.1% (2 of 2146 subjects/patients). Seizure incidence in clinical trials with doses of 450 mg/day was approximately 0.39% (2 of 537 subjects). There were no seizures in clinical trials where subjects (n=1638) were treated up to the maximum recommended dose of 300 mg/day. In post marketing data however, seizures have been observed across all doses and formulations of bupropion hydrochloride.
Predisposing Risk Factors for Seizures
The risk of seizure occurring with bupropion use appears to be associated with the presence of predisposing risk factors. Therefore, extreme caution should be used when treating patients with predisposing factors which increase the risk of seizures, including:
- Prior seizure (see 2 CONTRAINDICATIONS).
- History of head trauma.
- Central nervous system (CNS) tumour.
- The presence of severe hepatic impairment.
- Excessive use of alcohol; addiction to opiates, cocaine, or stimulants.
- Use of concomitant medications that lower seizure threshold, including but not limited to antipsychotics, antidepressants, lithium, amantadine, theophylline, systemic steroids, quinolone antibiotics, and anti-malarials.
- Use of over-the-counter stimulants or anorectics.
- Diabetes treated with oral hypoglycemics or insulin.
The above group of risk factors, including medications, should not be considered exhaustive; for each patient, all potential predisposing factors must be carefully considered.
In order to minimize the Risk of Seizure
The total daily dose of TARO-BUPROPION XL must not exceed 300 mg (the maximum recommended dose).
If a Seizure Occurs
Patients should be warned that if they experience a seizure while taking TARO-BUPROPION XL, they should contact their doctor or be taken to a hospital emergency ward immediately and should stop taking TARO-BUPROPION XL. Treatment should not be restarted if a patient has experienced a seizure while taking TARO-BUPROPION XL, bupropion hydrochloride sustained-release tablets, Contrave® or Zyban®.
- Serotonin Toxicity / Serotonin Syndrome
Serotonin toxicity, also known as serotonin syndrome, is a potentially life-threatening condition and has been reported with bupropion, including bupropion hydrochloride extended-release tablets, particularly during combined use with other serotonergic drugs (see 9.4 Drug-Drug Interactions).
Serotonin toxicity is characterized by neuromuscular excitation, autonomic stimulation (e.g. tachycardia, flushing) and altered mental state (e.g. anxiety, agitation, hypomania). In accordance with the Hunter Criteria, serotonin toxicity diagnosis is likely when, in the presence of at least one serotonergic agent, one of the following is observed:
- Spontaneous clonus
- Inducible clonus or ocular clonus with agitation or diaphoresis
- Tremor and hyperreflexia
- Hypertonia and body temperature >38°C and ocular clonus or inducible clonus.
If concomitant treatment with TARO-BUPROPION XL and serotonergic agents is clinically warranted, careful observation of the patient is advised, particularly during treatment initiation and dose increases (see 9.4 Drug-Drug Interactions). If serotonin toxicity is suspected, discontinuation of the serotonergic agents should be considered.
Ophthalmologic
- Angle-Closure Glaucoma
As with other antidepressants, TARO-BUPROPION XL can cause mydriasis, which may trigger an angle-closure attack in a patient with anatomically narrow ocular angles. Healthcare providers should inform patients to seek immediate medical assistance if they experience eye pain, changes in vision or swelling or redness in or around the eye.
Psychiatric
- Potential Association with Behavioural and Emotional Changes, Including Self-harm
Pediatrics: Placebo-Controlled Clinical Trial Data
Recent analyses of placebo-controlled clinical trial safety databases from SSRIs and other newer anti-depressants suggests that use of these drugs in patients under the age of 18 may be associated with behavioural and emotional changes, including an increased risk of suicidal ideation and behaviour over that of placebo.
The small denominators in the clinical trial database, as well as the variability in placebo rates, preclude reliable conclusions on the relative safety profiles among these drugs.
Adults and Pediatrics: Additional Data
There are clinical trial and post-marketing reports with SSRIs and other newer anti-depressants, in both pediatrics and adults, of severe agitation-type adverse events coupled with self-harm or harm to others. The agitation-type events include akathisia, agitation, disinhibition, emotional lability, hostility, aggression, depersonalization. In some cases, the events occurred within several weeks of starting treatment.
Rigorous clinical monitoring for suicidal ideation or other indicators of potential for suicidal behaviour is advised in patients of all ages given an anti-depressant drug. This includes monitoring for agitation-type emotional and behavioural changes.
- Clinical Worsening and Suicide
The possibility of a suicide attempt in seriously depressed patients is inherent to the illness and may persist until significant remission occurs. Patients with depression may experience worsening of their depressive symptoms and/or the emergence of suicidal ideation and behaviours (suicidality) whether or not they are taking antidepressant medications. As improvement may not occur during the first few weeks or more of treatment, patients should be closely monitored for clinical worsening (including development of new symptoms) and suicidality, especially at the beginning of a course of treatment, or at the time of dosage changes, either increases or decreases. Close supervision of high-risk patients should accompany initial drug therapy, and consideration should be given to the need for hospitalization (see Potential association with behavioural and emotional changes, including self-harm).
It should be noted that a causal role for SSRIs and other newer anti-depressants in inducing self-harm or harm to others has not been established.
In order to reduce the risk of overdose, prescriptions for TARO-BUPROPION XL (bupropion hydrochloride) should be written for the smallest number of tablets consistent with good patient management.
- Agitation and Insomnia
In placebo-controlled trials patients receiving bupropion hydrochloride sustained-release tablets experienced an increased incidence of insomnia and anxiety relative to those receiving placebo (see 8 ADVERSE REACTIONS and Potential association with behavioural and emotional changes, including self-harm). These symptoms were sometimes of sufficient magnitude to require discontinuation of bupropion hydrochloride sustained-release tablets, or concurrent treatment with sedative/hypnotic drugs. Insomnia may be minimized by avoiding bedtime doses and, if necessary, reduction in dose.
- Psychosis, Confusion, and Other Neuropsychiatric Phenomena
Patients treated with bupropion hydrochloride sustained-release tablets have been reported to show a variety of neuropsychiatric signs and symptoms including delusions, hallucinations, psychosis, concentration disturbance, paranoia and confusion. In some cases, these abated upon dose reduction and/or withdrawal of treatment.
- Activation of Psychosis and/or Mania
Antidepressants can precipitate manic episodes in bipolar patients during the depressed phase of their illness and may activate latent psychosis in other susceptible patients. TARO-BUPROPION XL is expected to pose similar risks.
Renal
- Hyponatremia
Hyponatremia cases have been reported very rarely with bupropion (see 8 ADVERSE REACTIONS). Caution should be exercised in patients at risk, such as elderly patients or patients concomitantly treated with medications known to cause hyponatremia.
- Renal Impairment
Bupropion is extensively metabolized in the liver to active metabolites, which are largely further metabolised before being excreted by the kidneys. TARO-BUPROPION XL treatment of patients with renal impairment should be initiated at a reduced dosage regimen, as metabolites may accumulate in such patients to a greater extent than usual. The patient should be closely monitored for possible adverse effects (eg., insomnia, dry mouth, seizures) that could indicate high drug or metabolite levels.
7.1 Special Populations
7.1.1 Pregnant Women
There are no adequate and well-controlled studies of bupropion hydrochloride extended-release tablets in pregnant women. TARO-BUPROPION XL should thus not be used during pregnancy unless the potential benefit is judged to outweigh the potential risk.
First Trimester Exposure
Data from pregnancy registries have documented congenital malformations including cardiovascular (e.g., ventricular and atrial septal defects) with maternal exposure to bupropion in the first trimester. Bupropion should be initiated during pregnancy or in women who intend to become pregnant only if benefits outweigh the potential risk to the fetus.
Third Trimester Exposure
Post-marketing reports indicate that some neonates exposed to SSRIs (Selective Serotonin Reuptake Inhibitors), or other newer anti-depressants, such as bupropion hydrochloride sustained-release tablets, late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. The frequency of symptoms may vary with each drug. These features are consistent with either a direct toxic effect of SSRIs and other newer anti-depressants, or, possibly, a drug discontinuation syndrome. When treating a pregnant woman with TARO-BUPROPION XL during the third trimester, the physician should carefully consider the potential risks and benefits of treatment (see 4.2 Recommended Dose and Dosage Adjustment).
7.1.2 Breast-feeding
Like many other drugs, bupropion and its metabolites are secreted in human milk. Because of the potential for serious adverse reactions in nursing infants from TARO-BUPROPION XL, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
7.1.3 Pediatrics
Based on the data submitted and reviewed by Health Canada, the safety and efficacy of bupropion hydrochloride extended-release tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use (see Potential association with behavioural and emotional changes, including self-harm and 4.2 Recommended Dose and Dosage Adjustment).
7.1.4 Geriatrics
Of the approximately 6000 patients who participated in clinical trials with bupropion sustained-release tablets (depression and smoking cessation studies), 275 were 65 and over and 47 were 75 and over. In addition, several hundred patients 65 and over participated in clinical trials using the immediate-release formulation of bupropion (depression studies). No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
A single-dose pharmacokinetic study demonstrated that the disposition of bupropion and its metabolites in elderly subjects was similar to that of younger subjects; however, another single and multiple dose pharmacokinetic study, has suggested that the elderly are at increased risk for accumulation of bupropion and its metabolites (see 10.3 Pharmacokinetics, Geriatrics).
Bupropion is extensively metabolized in the liver to active metabolites, of which some are eliminated by the kidney, while others are further metabolized before being excreted in urine. The risk of toxic reaction to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function (see Hepatic/Biliary/Pancreatic and Renal).
8 ADVERSE REACTIONS
8.1 Adverse Reaction Overview
The information included under ADVERSE REACTIONS is based on data from clinical trials with bupropion hydrochloride extended-release tablets, the once daily extended release formulation of bupropion in the treatment of major depressive disorder (MDD) and prevention of seasonal major depressive episodes. Information on additional adverse events associated with the sustained release formulation of bupropion as well as the immediate release formulation of bupropion, is included in a separate subsection (see 8.3 Less Common Clinical Trial Adverse Reactions).
Incidence of Commonly Observed Adverse Events in Controlled Clinical Trials
- Major Depressive Disorder
The most common adverse events encountered in bupropion hydrochloride extended-release tablets MDD clinical trials (incidence of ≥5% and higher incidence in bupropion hydrochloride extended-release tablets treated than placebo treated) were, dry mouth, nausea, constipation, insomnia, dizziness, anxiety, decreased appetite.
- Prevention of Seasonal Major Depressive Episodes
The most common adverse events encountered in bupropion hydrochloride extended-release tablets seasonal depression clinical trials (incidence of ≥5% and higher incidence with bupropion hydrochloride extended-release tablets than placebo) were , dry mouth, nausea, constipation, flatulence, headache, dizziness, insomnia, anxiety, nasopharyngitis, upper respiratory infection, and sinusitis.
Adverse Events Associated with Discontinuation of Treatment
- Major Depressive Disorder
In placebo-controlled studies in depression (411 patients treated with bupropion hydrochloride extended-release tablets, and 412 treated with placebo), adverse events caused discontinuation in 6% of bupropion hydrochloride extended-release tablets treated patients and 3% of placebo-treated patients. All adverse events leading to discontinuation of bupropion hydrochloride extended-release tablets occurred with an incidence of less than 1%.
- Prevention of Seasonal Major Depression Episodes
In placebo-controlled clinical trials, 9% of patients treated with bupropion hydrochloride extended-release tablets and 5% of patients treated with placebo discontinued treatment due to adverse events. The adverse events in these trials that led to discontinuation in at least 1% of patients treated with bupropion hydrochloride extended-release tablets and at a rate numerically greater than the placebo rate were insomnia (2% vs <1%) and headache (1% vs <1%).
Prospective Studies in Major Depressive Disorder Trials to Assess Drug-related Adverse Events on Sexual Function
Using identical protocols, studies AK130926 and AK130927 set orgasm dysfunction as a primary outcome measure, in addition to the HAMD-17 score. The studies compared the effects of bupropion hydrochloride extended-release tablets, placebo and a representative SSRI as a positive control, in a sample of depressed subjects with normal orgasmic function at baseline. Orgasm dysfunction, as defined by presence of orgasm delay, orgasm failure, or both, was based on investigator interview at the 0, 2, 4, 6- and 8-week points in the study.
In each of the two studies, AK130926 and AK130927, the percentage of subjects with orgasm dysfunction in the bupropion hydrochloride extended-release tablets groups (16% and 13%) were not significantly different from the placebo groups (8% and 11%). Statistically, these observed rates in both the placebo groups and the bupropion hydrochloride extended-release tablets groups were significantly lower as compared to the SSRI positive control groups (29% and 32%).
8.2 Clinical Trial Adverse Reactions
Clinical trials are conducted under very specific conditions. The adverse reaction rates observed in the clinical trials; therefore, may not reflect the rates observed in practice and should not be compared to the rates in the clinical trials of another drug. Adverse reaction information from clinical trials may be useful in identifying and approximating rates of adverse drug reactions in real-world use.
Major Depressive Disorder
Table 2 enumerates treatment-emergent adverse events that occurred at an incidence of 1% or more in placebo-controlled trials and were more frequent in the bupropion hydrochloride extended-release tablets group than the placebo group. Reported Adverse Events were classified using MedDRA. (Treatment-Emergent adverse events related to sexual function were assessed using specific outcome measures in two placebo-controlled studies - see 8.1 Adverse Reaction Overview).
Table 2: Treatment Emergent Adverse Events Incidence in Major Depressive Disorder Placebo-Controlled Studies (pooled results)
| System Organ Class / Preferred Term | Bupropion Hydrochloride Extended-Release Tablets (n = 411) (%) | Placebo (n = 412) (%) |
Cardiac Disorders Palpitations | 13 (3%) | 10 (2%) |
Ear and Labyrinth Disorders Tinnitus | 11 (3%) | 3 (<1%) |
Eye Disorders Vision Blurred | 8 (2%) | 4 (<1%) |
Gastrointestinal Disorders Nausea Dry Mouth Constipation Abdominal Pain Upper Vomiting Abdominal Pain | 63 (15%) 79 (19%) 41 (10%) 17 (4%) 10 (2%) 6 (1%) | 42 (10%) 38 (9%) 27 (7%) 7 (2%) 8 (2%) 5 (1%) |
General Disorders Feeling Jittery Pyrexia Chest Pain Chest Discomfort | 9 (2%) 5 (1%) 5 (1%) 5 (1%) | 6 (1%) 4 (<1%) 2 (<1%) 0 |
Infections and Infestations Nasopharyngitis Influenza | 16 (4%) 8 (2%) | 11 (3%) 6 (1%) |
Investigations Weight decreased Heart Rate Increased | 8 (2%) 6 (1%) | 1 (<1%) 0 |
Metabolism and Nutrition Decreased appetite | 19 (5%) | 14 (3%) |
Musculoskeletal Disorders and Connective Tissue Myalgia | 10 (2%) | 7 (2%) |
Nervous System Disorders Dizziness Tremor Dysgeusia | 32 (8%) 17 (4%) 12 (3%) | 15 (4%) 4 (<1%) 2 (<1%) |
Psychiatric Disorders Insomnia Irritability Anxiety Restlessness Initial Insomnia Middle insomnia Panic Attack | 40 (10%) 17 (4%) 21 (5%) 11 (3%) 5 (1%) 5 (1%) 5 (1%) | 17 (4%) 16 (4%) 8 (2%) 8 (2%) 4 (<1%) 3 (<1%) 1 (<1%) |
Respiratory Disorders, Thoracic and Mediastinal Cough | 10 (2%) | 6 (1%) |
| System Organ Class / Preferred Term | Bupropion Hydrochloride Extended-Release Tablets (n = 411) (%) | Placebo (n = 412) (%) |
Skin and Subcutaneous Tissue Disorders Rash Rash Hyperhidrosis Pruritus | 11 (3%) 9 (2%) 6 (1%) | 5 (1%) 5 (1%) 5 (1%) |
Vascular Disorders Hot Flush Hypertension | 5 (1%) 5 (1%) | 2 (<1%) 3 (<1%) |
Prevention of Seasonal Major Depression Episodes
Table 3 enumerates treatment-emergent adverse events that occurred at an incidence of 1% or more in placebo-controlled trials and were more frequent in the bupropion hydrochloride extended-release tablets group than the placebo group.
Table 3: Treatment Emergent Adverse Events Incidence in Prevention of Seasonal Major Depression Episodes Placebo-Controlled Studies (pooled results)
| System Organ Class / Preferred Term | Bupropion Hydrochloride Extended-Release Tablets (n = 511) (%) | Placebo (n = 537) (%) |
Ear and Labyrinth Disorders Tinnitus | 18 (3 %) | 3 (<1%) |
Eye Disorders Vision Blurred | 7 (1%) | 3 (<1%) |
Gastrointestinal Disorders Dry mouth Nausea Constipation Flatulence Abdominal pain Toothache | 137 (26%) 68 (13%) 47 (9%) 30 (6%) 11 (2%) 8 (1%) | 79 (15% 39 (8%) 10 (2%) 17 (3%) 2 (<1%) 5 (<1%) |
General Disorders Feeling Jittery Thirst Chest pain | 17 (3%) 6 (1%) 6 (1%) | 8 (2%) 3 (<1%) 2 (<1%) |
Infections and Infestations Nasopharyngitis Upper respiratory tract infection Sinusitis Urinary tract infection Pharyngitis streptococcal | 71 (13%) 47 (9%) 27 (5%) 8 (1%) 6 (1%) | 62 (12%) 43 (8%) 20 (4%) 5 (<1%) 3 (<1%) |
Metabolism and Nutrition Decreased appetite | 20 (4%) | 6 (1%) |
| System Organ Class / Preferred Term | Bupropion Hydrochloride Extended-Release Tablets (n = 511) (%) | Placebo (n = 537) (%) |
Musculoskeletal and Connective Tissue Disorders Myalgia Pain in extremity Muscle spasms | 14 (3%) 14 (3%) 7 (1%) | 11 (2%) 10 (2%) 1 (<1%) |
Nervous System Disorders Headache Dizziness Tremor Dysgeusia Memory impairment | 182 (34%) 31 (6%) 18 (3%) 8 (1%) 6 (1%) | 138 (27%) 23 (5%) 6 (1%) 3 (<1%) 0 |
Psychiatric Disorders Insomnia Anxiety Middle insomnia Abnormal dreams Agitation Initial insomnia Disturbance in attention | 84 (16%) 28 (5%) 12 (2%) 11 (2%) 11 (2%) 11 (2%) 7 (1%) | 58 (11%) 22 (4%) 7 (1%) 5 (<1%) 4 (<1%) 3 (<1%) 4 (<1%) |
Reproductive System and Breast Disorders Dysmenorrhoea | 11 (2%) | 2 (<1%) |
Respiratory, Thoracic and Mediastinal Disorders Cough Dyspnoea | 21 (4%) 8 (1%) | 16 (3%) 2 (<1%) |
Skin and Subcutaneous Tissue Disorders Rash Acne Pruritis Urticaria | 14 (3%) 8 (1%) 7 (1%) 7 (1%) | 11 (2%) 1 (<1%) 4 (<1%) 0 |
Vascular Disorders Hypertension Hot flush | 10 (2%) 7 (1%) | 0 1 (<1%) |
In addition to the events noted above for Bupropion Hydrochloride Extended-Release Tablets, the following adverse events have been reported in clinical trials with the sustained release formulation of bupropion in depressed patients and in non-depressed smokers, as well as in clinical trials with the immediate release formulation of bupropion.
Seizures
At doses of bupropion hydrochloride sustained-release tablets up to a dose of 300 mg/day, the incidence of seizure is approximately 0.1% (1/1,000) and increases to approximately 0.4% (4/1000) at a dose of 400 mg/day. Data for the immediate release bupropion revealed a seizure incidence of approximately 0.4% (13 of 3,200 patients followed prospectively) in patients treated at doses of 225 to 450 mg/day. Additional data accumulated for the immediate release formulation of bupropion suggests that the estimated seizure incidence increases almost tenfold between 450 and 600 mg/day. The 600 mg dose is twice the adult dose of bupropion hydrochloride extended-release tablets. This disproportionate increase in seizure incidence with dose incrementation calls for caution in dosing.
Adverse Events Associated with Discontinuation of Treatment with Other Formulations
In placebo-controlled studies of depression with bupropion hydrochloride sustained-release tablets (987 patients treated, and 385 treated with placebo) adverse events caused discontinuation in 7% of bupropion hydrochloride sustained-release tablets-treated patients and 3% of placebo-treated patients. The more common events leading to discontinuation of bupropion hydrochloride sustained-release tablets included nervous system disturbances (2.2%), primarily agitation, anxiety and insomnia; skin disorders (1.9%), primarily rashes, pruritis, and urticaria; general body complaints (1.0%), primarily headaches, and digestive system disturbances (1.0%), primarily nausea. Two patients in bupropion hydrochloride sustained-release tablets treatment groups discontinued due to hallucinations (auditory or visual). The rates of premature discontinuation due to an adverse event were dose-related in these studies.
In an open label, uncontrolled (acute treatment and continuation) study of bupropion hydrochloride sustained-release tablets, 11% patients (361 out of 3100) discontinued treatment due to an adverse event. Adverse events leading to premature discontinuation in 1% or more of patients were: headache (1.1%), nausea (1.0%), and insomnia (1.0%). Adverse events leading to premature discontinuation in 0.5% to 1% of patients were: anxiety (0.8%), rash (0.8%), agitation (0.7%), irritability (0.5%), and dizziness (0.5%). In those patients (n = 1577) who went into the continuation phase after 8 weeks of treatment, 6 (0.4%) discontinued due to alopecia. Because this study was uncontrolled, it is not possible to reliably assess the causal relationship of these events to treatment with bupropion hydrochloride sustained-release tablets.
Adverse Events Occurring at an Incidence of 1% or More Among Patients Treated with
Bupropion Hydrochloride Sustained-Release Tablets in Placebo Controlled trials:
Table 4 enumerates treatment-emergent adverse events that occurred at an incidence of 1% or more and were more frequent than in the placebo group, in patients participating in placebo-controlled clinical trials. Reported adverse events were classified using a COSTART-based Dictionary.
Table 4 - Treatment Emergent Adverse Events Occurring in ≥1% of Patients in Any BUP
SR Group for Studies 203, 205, and 212
| System Organ Class / Preferred Term | % AEs BUP SR 100- 150 (n=382) | %AEs BUP SR 200- 300 (n=491) | %AEs PBO (n = 385) |
General Disorders Asthenia Pain Chest Pain | 1.8 1.3 1 | 1.6 2.4 2.9 | 1.6 2.1 0.8 |
Cardiac Disorders Palpitations Tachycardia | 2.9 1.6 | 2 0.6 | 1.6 0.5 |
| System Organ Class / Preferred Term | % AEs BUP SR 100- 150 (n=382) | %AEs BUP SR 200- 300 (n=491) | %AEs PBO (n = 385) |
Ear and Labyrinth Disorders Tinnitus | 3.9 | 5.1 | 1.8 |
Eye Disorders Amblyopia | 2.9 | 2.4 | 1.8 |
Gastrointestinal Disorders Abdominal Pain Constipation Diarrhoea Dry Mouth Dyspepsia Flatulence Nausea Vomiting | 3.9 6.5 3.9 13.1 4.2 1.8 10.7 1.8 | 3.5 10.8 5.9 16.5 4.7 3.1 12.6 3.9 | 1.6 6.8 5.7 7 4.4 2.1 7.5 1.6 |
Infections and Infestations Influenza Infection | 6.2 4.7 | 2.4 7.5 | 3.1 6.5 |
Injury, Poisoning and Procedural Complications Injury | 1.8 | 1.8 | 1.8 |
Metabolism and Nutrition Disorders Decreased Appetite | 3.1 | 4.5 | 1.6 |
Musculoskeletal and Connective Tissue Disorders Arthralgia Back Pain Muscle Spasms Myalgia Muscle Twitching Neck Pain | 2.6 1.8 1 1.6 0.8 1.3 | 0.8 4.5 0.2 3.3 1 2 | 0.5 3.1 0.5 2.9 0.3 1.3 |
Ne rv ous Syste m Disorders Dizziness Dysgeusia Headache Hypertonia Migraine Somnolence Tremor | 7.1 1 27.5 1 0.8 2.6 3.1 | 8.6 1.4 26.9 1.2 1.4 2.0 6.1 | 5.5 0.3 23.4 0.5 1 2.1 0.8 |
Psychiatric Disorders Agitation Anxiety Insomnia Irritability Libido Decreased Nervousness | 1.6 4.5 7.9 2.4 1 4.5 | 3.5 4.3 11.4 3.9 0.6 4.1 | 1.8 3.1 6.5 1.6 0.5 2.6 |
| System Organ Class / Preferred Term | % AEs BUP SR 100- 150 (n=382) | %AEs BUP SR 200- 300 (n=491) | %AEs PBO (n = 385) |
Re spiratory, Thoracic and Mediastinal Disorders Pharyngitis Rhinitis Sinusitis | 1.3 9.9 1.6 | 2.9 6.7 2.4 | 1.8 9.6 2.1 |
Skin and Subcutaneous Tissue Disorders Pruritus Rash Hyperhidrosis Urticaria | 2.4 2.1 2.4 0.8 | 2.2 4.1 5.1 1.4 | 1.6 1.3 1.6 0 |
Surgical and Medical Procedures Central Nervous System Stimulation | 0 | 1.2 | 0.5 |
Renal and Urinary Disorders Urinary Tract Infection Pollakiuria | 1 1.3 | 1.8 2.4 | 0.3 1.6 |
Vascular Disorders Hot Flush | 1.3 | 1 | 0.8 |
8.3 Less Common Clinical Trial Adverse Reactions
The following treatment-emergent adverse drug reactions were reported with <1% incidence in the three pooled MDD, and the three pooled seasonal depression bupropion hydrochloride extended-release tablets clinical trials. The extent to which these events may be associated with bupropion hydrochloride extended-release tablets is unknown.
Blood and Lymphatic System Disorders: Lymphadenopathy, anaemia.
Cardiovascular Disorders: Cardiac flutter, tachycardia, supraventricular tachycardia.
Ear and Labyrinth Disorders: Ear pain, motion sickness, vertigo, hyperacusis.
Eye Disorders: Eye pruritus, conjunctivitis, eye pain, dry eye, dacryostenosis acquired, lacrimation decreased, lacrimation increased, photophobia, vitreous floaters.
Gastrointestinal Disorders: diarrhoea, abdominal discomfort, gastroesophageal reflux disease, frequent bowel movements, abdominal pain lower, eructation, gastritis, breath odour, epigastric discomfort, hyperchlorhydria, oral hypoaesthesia, lip dry, pancreatitis, abdominal distension, food poisoning, defaecation urgency, duodenal ulcer haemorrhage, gastrointestinal pain, gingival pain, gingivitis, infrequent bowel movements, mouth ulceration, oral pain.
General Disorders and Administration Site Conditions: Pain, oedema peripheral, asthenia, feeling abnormal, feeling hot, influenza like illness, thirst, energy increased, hunger, malaise, rigors, respiratory sighs, energy increased, feeling cold, impaired healing, injection site joint pain, temperature intolerance.
Immune System Disorders: seasonal allergy, drug hypersensitivity, rubber sensitivity, hypersensitivity, food allergy.
Infections and Infestations: bronchitis, fungal infection, ear infection, gastroenteritis, bacterial vulvovaginitis, cystitis, herpes zoster, pharyngitis, vulvovaginal mycotic infection, wound infection, conjunctivitis, dental caries, herpes virus infection, hordeolum, localised infection, viral upper respiratory tract infection, respiratory tract infection, rhinitis, tooth infection, laryngitis, tooth abscess, pneumonia, folliculitis, viral gastritis, hepatitis C, prostate infection, tinea pedis, tonsillitis.
Injury, Poisoning and Procedural Complications: contusion, ligament sprain, muscle strain, skin laceration, skin abrasion, procedural pain, limb injury, sunburn, accidental overdose, arthropod bite, facial bones fracture, mouth injury, soft tissue injury, wrist fracture, back injury, joint injury, epicondylitis, concussion, fall, animal scratch, skin laceration, lower limb fracture.
Investigations: blood pressure increased, weight increased, heart rate irregular.
Metabolism and Nutrition Disorders: decreased appetite, food craving, increased appetite, dehydration, hypercholesterolaemia.
Musculoskeletal and Connective Tissue Disorders: muscle tightness, neck pain, muscle twitching, pain in jaw, musculoskeletal stiffness, muscle spasms, sensation of heaviness, tendonitis, musculoskeletal chest pain, musculoskeletal pain, bursitis, flank pain, joint stiffness, joint swelling, muscular weakness, osteoporosis, tendon disorder.
Neoplasms, (Benign, Malignant and Unspecified (incl. Cysts and Polyps): basal cell carcinoma, cyst, breast cancer.
Nervous System Disorders: Amnesia, depressed level of consciousness, disturbance in attention, dyslexia, sinus headache, hypersomnia, hypoaesthesia, lethargy, migraine, muscle contractions involuntary, myoclonus, paraesthesia, paraesthesia oral, parosmia, sedation, tension headache, psychomotor hyperactivity, somnolence, carpal tunnel syndrome, nerve compression, sensory disturbance, hypotonia, sciatica.
Psychiatric Disorders: Aggression, affect lability, anger, bruxism, confusional state, crying, depersonalization/derealisation disorder, depressed mood, depressive symptom, disturbance in sexual arousal, terminal insomnia, euphoric mood, feeling of despair, feelings of worthlessness, hallucination, auditory hallucination, mood altered, mood swings, nervousness, abnormal orgasm, paranoia, sleep disorder, tension, thinking abnormal, trichotillomania, libido decreased, nightmare, restlessness, panic reaction, disorientation, hostility, psychomotor hyperactivity, stress, apathy, delusion, mood altered, perseveration, somnambulism, social avoidant behaviour.
Renal and Urinary Disorders: Micturition urgency, urethral pain, dysuria, hypertonic bladder, micturition disorder, polyuria, renal pain, urinary incontinence.
Reproductive System and Breast Disorders: intermenstrual bleeding, menstruation irregular, amenorrhoea, genital rash, premenstrual syndrome, erectile dysfunction, menstrual disorder, breast tenderness, testicular pain, breast calcifications, breast enlargement, nipple pain, ovarian cyst, vaginal haemorrhage.
Respiratory, Thoracic, and Mediastinal Disorders: Asthma, dyspnoea, epistaxis, increased upper airway secretion, respiratory tract congestion, rhinorrhea, sinus disorder, sneezing, throat irritation, vocal cord disorder, yawning, sinus pain, hyperventilation, snoring, nasal dryness, pleuritic pain, pulmonary congestion, wheezing.
Skin and Subcutaneous Tissue Disorders: Alopecia, cold sweat, dermal cyst, dry skin, increased tendency to bruise, night sweats, photosensitivity reaction, rash erythematous, skin irritation, urticaria, eczema, face oedema, hypotrichosis, pruritus, swelling face, circumoral oedema, dermatitis allergic, rash pruritic, sebaceous gland disorder.
Vascular Disorders: Flushing, peripheral coldness.
Less Common bupropion hydrochloride sustained-release tablets Clinical Trial Adverse Drug Reactions (<1%) Events Observed During Development and Post -Marketing Experience of Bupropion with Other Formulations or Indications
Adverse events for which frequencies are provided below occurred in clinical trials with the sustained-release formulation of bupropion. The frequencies represent the proportion of patients who experienced a treatment-emergent adverse event on at least one occasion in placebo-controlled studies for depression (n = 987) or smoking cessation (n = 1013), or patients who experienced an adverse event requiring discontinuation of treatment in an open - label surveillance study with bupropion hydrochloride sustained-release tablets (n = 3100). All treatment-emergent adverse events are included except those listed in Table 4, those events listed in other safety - related sections, those adverse events subsumed under COSTART terms that are either overly general or excessively specific so as to be uninformative, those events not reasonably associated with the use of the drug, and those events that were not serious and occurred in fewer than two patients.
Events of major clinical importance are described in the 7 WARNINGS AND PRECAUTIONS sections of the labelling.
Events are further categorized by body system and listed in order of decreasing frequency according to the following definitions of frequency: Frequent adverse events are defined as those occurring in at least 1/100 patients. Infrequent adverse events are those occurring in
1/100 to 1/1000 patients, while rare events are those occurring in less than 1/1000 patients.
Adverse events for which frequencies are not provided occurred in clinical trials or post marketing experience with bupropion. Only those adverse events not previously listed for sustained-release bupropion are included. The extent to which these events may be associated with bupropion hydrochloride sustained-release tablets is unknown.
Blood and Lymphatic System Disorders:
Infrequent was ecchymosis.
Also observed were anaemia, leukocytosis, leukopenia, lymphadenopathy, pancytopenia, and thrombocytopenia.
Cardiac Disorders:
Rare was syncope.
Also observed were atrioventricular block complete, extrasystoles and myocardial infarction.
Endocrine Disorders:
Also observed were hyperglycemia, hypoglycemia, and inappropriate antidiuretic hormone secretion.
Eye Disorders:
Infrequent were accommodation disorder and dry eye.
Also observed were diplopia and mydriasis.
Gastrointestinal Disorders:
Infrequent were bruxism, gastroesophageal reflux, gingivitis, glossitis, salivary hypersecretion, mouth ulcerations, and stomatitis.
Rare was tongue oedema.
Also observed were colitis, oesophagitis, gastrointestinal haemorrhage, gingival bleeding, intestinal perforation, pancreatitis, and gastric ulcer.
General Disorders:
Infrequent were chills, face oedema and thirst.
Rare was malaise.
Also observed was pyrexia.
Hepatobiliary Disorders:
Infrequent were abnormal liver function and jaundice.
Also observed were hepatitis and liver injury
Investigations:
Also observed was electroencephalogram abnormal
Metabolism and Nutrition Disorders:
Infrequent were oedema and peripheral oedema.
Very rare was hyponatremia.
Musculoskeletal and Connective Tissue Disorders:
Infrequent were musculoskeletal chest pain.
Also observed were arthritis, muscle rigidity/pyrexia, rhabdomyolysis and muscle weakness.
Nervous System Disorders:
Infrequent were abnormal coordination, cerebrovascular accident, hyperkinesia, hypoaesthesia and vertigo.
Rare were amnesia and ataxia.
Also observed were akinesia, aphasia, coma, dysarthria, dyskinesia, dystonia, extrapyramidal syndrome, hypokinesia, neuralgia, neuropathy peripheral, serotonin syndrome and tardive dyskinesia.
Psychiatric Disorders:
Infrequent were depersonalisation/derealisation disorder, dysphoria, affect lability, hostility and suicidal ideation.
Rare were derealisation and hypomania.
Also observed were delirium, euphoric mood, hallucinations, libido increased, mania and paranoia
Renal and Urinary Disorders:
Also observed was glycosuria.
Reproductive System and Breast Disorders:
Infrequent were erectile dysfunction and prostatic disorder.
Also observed were ejaculation disorder, dyspareunia, gynaecomastia, menopause, painful erection, salpingitis and vaginal infection
Respiratory, Thoracic and Mediastinal Disorders:
Rare were bronchospasm and dyspnea.
Also observed were pneumonia and epistaxis.
Skin and Subcutaneous Tissue Disorders:
Infrequent was photosensitivity reaction.
Rare was rash maculo-papular.
Also observed were alopecia, hirsutism, angioedema, exfoliative dermatitis, erythema multiforme, and Stevens-Johnson syndrome. Arthralgia, myalgia and fever have also been reported in association with rash and other symptoms suggestive of delayed hypersensitivity. These symptoms may resemble serum sickness.
Surgical and Medical Procedures:
Infrequent was vasodilation.
Renal and Urinary Disorders:
Infrequent was polyuria.
Also observed were cystitis, dysuria, urinary incontinence and urinary retention.
Vascular Disorders:
Infrequent was orthostatic hypotension.
Also observed were hypotension, hypertension (in some cases severe, see Cardiovascular), phlebitis and pulmonary embolism.
8.5 Post-Market Adverse Reactions
In addition to the events noted above, the following adverse events have been reported in post-market experience with the extended release formulation of bupropion in depressed patients and in non-depressed smokers, as well as in post-market experience with the immediate release formulation of bupropion. Only those adverse events not previously listed are included.
Cardiac Disorders: Brugada syndrome
Nervous System Disorders:
Dysphemia: Post-marketing reports suggest a link between dysphemia and bupropion hydrochloride extended-release tablets. Symptoms typically resolve upon discontinuation and may reappear with rechallenge. Patients with a history of dysphemia may experience exacerbation of symptoms.
Seizures: Post-marketing reports suggest that the reintroduction of bupropion hydrochloride extended-release tablets in patients who experienced a seizure is associated with a risk of seizure reoccurrence in some cases. Thus, patients should not restart bupropion hydrochloride extended-release tablets therapy if they have had a seizure on a bupropion formulation (bupropion hydrochloride extended-release tablets, bupropion hydrochloride sustained-release tablets, Contrave® OR Zyban®) (see Seizures).
Skin and Subcutaneous Tissue Disorders
Very rare cases have been observed for acute generalised exanthematous pustulosis (AGEP).
9 DRUG INTERACTIONS
9.1 Serious Drug Interactions
9.2 Drug Interactions Overview
In vitro studies indicate that bupropion is primarily metabolized to hydroxybupropion by the CYP2B6 isoenzyme (see Metabolism). Therefore, the potential exists for a drug interaction between bupropion hydrochloride extended-release tablets and drugs that affect the CYP2B6 isoenzyme (e.g., orphenadrine, cyclophosphamide, ifosfamide, ticlopidine, and clopidogrel). The threohydrobupropion metabolite of bupropion does not appear to be produced by the cytochrome P450 isoenzymes. Few systematic data have been collected on the metabolism of bupropion following concomitant administration with other drugs or alternatively, the effect of concomitant administration of bupropion hydrochloride sustained-release tablets on the metabolism of other drugs.
Following chronic administration of bupropion, 100 mg t.i.d. to 8 healthy male volunteers for 14 days, there was no evidence of induction of its own metabolism.
Because bupropion is extensively metabolized, the coadministration of other drugs may affect its clinical activity. In particular, certain drugs may induce the metabolism of bupropion (e.g.,
Serious Drug Interactions
Serious drug interactions with bupropion hydrochloride extended-release tablets include:
- concomitant medicines that contain bupropion hydrochloride (e.g., bupropion hydrochloride sustained-release tablets, Zyban®, and Contrave®);
- monoamine oxidase inhibitors (MAOI);
- medicines that contain thioridazine.
See 2 CONTRAINDICATIONS for details.
carbamazepine, phenobarbital, phenytoin, ritonavir, efavirenz).
9.3 Drug-Behavioural Interactions
Alcohol Interactions
In post-marketing experience, there have been reports of adverse neuropsychiatric events, or reduced alcohol tolerance, in patients who were drinking alcohol during treatment with bupropion. Rarely, reports of fatal outcomes with this combination have been received, however a causal relationship has not been established. The consumption of alcohol during treatment with bupropion should be avoided (also see Seizures).
9.4 Drug-Drug Interactions
The drugs listed in this table are based on either drug interaction case reports or studies, or potential interactions due to the expected magnitude and seriousness of the interaction (i.e., those identified as contraindicated).
Table 5 - Established or Potential Drug-Drug Interactions with bupropion hydrochloride extended-release tablets
| Proper/Common name | Source of Evidence | Effect | Clinical comment |
Drugs Metabolized by CYP2D6 including most antidepressants (SSRIs, many tricyclics), beta-blockers, antiarrhythmics | CT | ↓ CYP2D6 isoenzyme Bupropion and hydroxybupropion are inhibitors of the CYP2D6 isoenzyme in vitro. In 15 male subjects (aged 19 to 35 years) who were extensive metabolizers of CYP2D6, daily doses of bupropion given as 150 mg twice daily, followed by a single dose of 50 mg desipramine, increased the Cmax, AUC, and t1/2 of desipramine by an average of approximately two-, five- and two-fold, respectively. The effect was present for at least 7 days after the last dose of bupropion. | Concomitant therapy with drugs predominately metabolized by CYP2D6 should be initiated at the lower end of the dose range of the concomitant medication. If bupropion is added to the treatment regimen of a patient already receiving a medication metabolized by CYP2D6, the need to decrease the dose of the original medication should be considered, particularly for those medications with a narrow therapeutic index. |
| Tamoxifen (a pro-drug requiring metabolic activation by CYP2D6) | T | ↓ efficacy of tamoxifen | Co-administration of Tamoxifen with strong CYP2D6 inhibitors such as bupropion can lead to reduced plasma concentrations of a primary active metabolite (endoxifen) which may result in reduced efficacy of tamoxifenBupropion should not be used in combination with tamoxifen and other treatment options should be considered (see Drugs Metabolized by Cytochrome P450 (CYP2D6)). |
| Citalopram | CT | ↑ Cmax and AUC of citalopram | In a 3-period, sequential-treatment, crossover study in 30 healthy volunteers), bupropion increased the Cmax and AUC of citalopram by 30% and 40% respectively. Citalopram did not significantly alter the pharmacokinetics of bupropion. |
Ritonavir/Lopinavir/ Efavirenz | CT | ↓ bupropion AUC 20 - 80% ↓ bupropion AUC 55% In an open-label, two-phase, sequential study of 64 healthy volunteers, ritonavir (100 mg twice daily or 600 mg twice daily) or ritonavir 100 mg plus lopinavir 400 mg twice daily reduced the exposure of bupropion (150 - 300 mg daily) and its major metabolites in a dose dependent manner by approximately 20 to 80%. Similarly, efavirenz 600 mg once daily for two weeks reduced the exposure of a single oral 150 mg dose of bupropion by approximately 55% in 13 healthy volunteers (18 - 55 years of age). | Patients receiving ritonavir, lopinavir or efavirenz with bupropion may need increased doses of bupropion, but the maximum recommended daily dose of bupropion should not be exceeded. The effects of bupropion on the PK parameters of ritonavir/ lopinavir and efavirenz have not been studied. |
Co-administration of Thioridazine Contraindicated | T | ↓ inhibition of thioridazine metabolism | Administration of the antipsychotic thioridazine alone produces prolongation of the QTc interval, which is associated with serious ventricular arrhythmias such as torsades de pointes, and sudden death. As this effect appears to be dose-related, it is anticipated that risk increases with inhibition of thioridazine metabolism. An in-vivo study suggests that drugs which inhibit CYP2D6 will elevate plasma levels of thioridazine. Therefore, concomitant use of thioridazine with TARO-BUPROPION XL is contraindicated (see 2 CONTRAINDICATIONS). |
| MAO Inhibitors | T | ↑ acute toxicity of bupropion | Studies in animals demonstrate that the acute toxicity of bupropion is enhanced by the MAO inhibitor, phenelzine (see 2 CONTRAINDICATIONS). |
| Cimetidine | CT | ↑ combined threohydro and erythrobupropion AUC (16%) and Cmax (32%) | The effects of concomitant administration of cimetidine on the pharmacokinetics of bupropion and its active metabolites were examined in a crossover study in 24 healthy young male volunteers, following oral administration of two 150 mg bupropion hydrochloride sustained-release tablets with and without 800 mg of cimetidine. A single dose of cimetidine had no effect on single dose pharmacokinetic parameter estimates for bupropion, or hydroxybupropion, but caused a small statistically significant increase in the combined threohydro and erythrobupropion AUC (16%) and Cmax (32%). |
| Lamotrigine | CT | ↑ AUC of its metabolite | In a randomized, cross-over study of 12 healthy volunteers, multiple 150 mg bid oral doses of bupropion sustained release formulation had no statistically significant effect on the single (100 mg) dose pharmacokinetics of lamotrigine and had only a 15% increase in the AUC of its metabolite (lamotrigine glucuronide), which is not considered clinically significant. The effect(s) of lamotrigine on pharmacokinetics of bupropion is unknown. |
Levodopa and Amantadine | CT | ↑ incidence of neuropsychiatric adverse experiences | Limited clinical data suggest a higher incidence of neuropsychiatric adverse experiences, such as confusion, agitation and delirium, in patients receiving bupropion, concurrently with either levodopa or amantadine. Tremor, ataxia and dizziness were also reported. Administration of TARO-BUPROPION XL to patients receiving either levodopa or amantadine concurrently should be undertaken with caution, using small initial doses and gradual dose increases. |
Clopidogrel and Ticlopidine | CT | ↑ plasma concentrations of bupropion and ↓ concentrations of hydroxybupropion The mean area under the plasma concentration-time curve (AUC) of hydroxybupropion was reduced by 52% by clopidogrel and by 84% by ticlopidine. The AUC of bupropion was increased by 60% with clopidogrel and by 85% with ticlopidine. | Both clopidogrel and ticlopidine have been shown to significantly inhibit CYP2B6-catalysed bupropion hydroxylation. This may affect the efficacy of bupropion and may also increase the risk of concentration-dependent adverse events of bupropion, such as seizures (see Seizures). Patients receiving either clopidogrel or ticlopidine are likely to require dose adjustments of bupropion. |
| Digoxin | CT | ↓ digoxin AUC0-24h and increases renal clearance A clinical report suggests that when administered ~24 hours before digoxin, bupropion (extended-release, 150 mg) decreases digoxin AUC0-24h 1.6-fold and increases renal clearance 1.8-fold in healthy volunteers. | Co-administration of digoxin with bupropion may decrease digoxin levels. Monitor digoxin levels in patients treated concomitantly with bupropion and digoxin. Clinicians should be aware that digoxin levels may rise on discontinuation of bupropion and the patient should be monitored for possible digoxin toxicity. |
| Drugs that Predispose Patients to Seizures | T | Concurrent administration of TARO-BUPROPION XL Tablets with agents that lower seizure threshold (e.g., antipsychotics, other antidepressants, theophylline, lithium, systemic steroids, etc.) should be undertaken only with extreme caution (see Seizures). Low initial dosing and gradual dose increases should be employed. | |
Other Drugs with CNS Activity | T | The risk of using Bupropion Hydrochloride Extended-Release Tablets TARO-BUPROPION XL in combination with other CNS- active drugs has not been systematically evaluated. Consequently, caution is advised if the concomitant administration of TARO-BUPROPION XL and such drugs is required. | |
Transdermal Nicotine Interaction | CT | (see Cardiovascular) | |
| SSRIs/SNRIs | C | ↑ Serotonin | Increased risk of Serotonin toxicity (see Serotonin toxicity/Serotonin Syndrome) |
Legend: C = Case Study; CT = Clinical Trial; T = Theoretical
9.5 Drug-Food Interactions
Interactions of Bupropion Hydrochloride Extended-Release Tablets with food have not been established.
9.6 Drug-Herb Interactions
Interactions of Bupropion Hydrochloride Extended-Release Tablets with herbal have not been established.
9.7 Drug- Laboratory Test Interactions
Interactions of Bupropion Hydrochloride Extended-Release Tablets with laboratory tests have not been established.
10 CLINICAL PHARMACOLOGY
10.1 Mechanism of Action
Bupropion hydrochloride extended-release tablets are an atypical antidepressant of the aminoketone class with mild CNS activating properties. It is chemically unrelated to tricyclic, tetracyclic, SSRIs or other known antidepressant agents. Its structure closely resembles that of diethylpropion. It is related to the phenylethylamines.
The mechanism of bupropion’s antidepressant activity is unknown but appears to be mediated by noradrenergic (and possibly dopaminergic), rather than serotonergic mechanisms. Preclinical studies have shown that bupropion blocks norepinephrine (NE) reuptake and dopamine (DA) reuptake. Its major metabolite (hydroxybupropion), which in man is present at blood levels 10-20-fold higher than bupropion, blocks only NA reuptake.
As with other antidepressants, bupropion and hydroxybupropion reduce firing rates of NE neurons in the locus coeruleus. This effect is dependent on presynaptic stores of NE and can be blocked by α-adrenergic antagonists. The mild stimulating properties of bupropion appear to be due to its weak inhibition of dopamine (DA) uptake. This effect occurs at doses higher than those needed for antidepressant activity. The drug has no pharmacologically relevant effects on serotonin (5-HT).
The non-serotonergic mechanism of action of bupropion likely contributes to a distinct side effect profile that includes low rates of sexual dysfunction and somnolence (see 8.1 Adverse Reaction Overview).
10.2 Pharmacodynamics
In vitro, bupropion and its major metabolites had essentially no affinity for β-adrenergic, dopaminergic, GABA, benzodiazepine, 5HT1A, glycine and adenosine receptors, and only weakly inhibited α-adrenergic receptors in rat brain, α2-adrenergic, 5HT2, and muscarinic cholinergic receptors. High concentrations of bupropion and its major metabolites did not inhibit MAO-A or MAO-B activity. Bupropion and its major metabolites had no significant affinity for the 5HT transport system.
Large i.v. doses of bupropion had no sustained adverse effects on the cardiovascular system of dogs (13-50 mg/kg cumulative) and cats (18.5 mg/kg). Transient (<10 min) significant, dose-dependent decreases in mean arterial pressure and cardiac output with variable effects on heart rate were observed following bolus IV injections; the effects were much greater following bolus administration than following equivalent infused doses. The effects were most likely related to the transient high plasma levels (approximately 10-fold higher than both therapeutic plasma levels in man and plasma levels associated with the mouse antidepressant ED50) and the local anesthetic-like activity. At all dose levels studied, effects on the ECG were entirely related to heart rate; there were no changes in the PR, QRS or QTC intervals. No arrhythmias were observed.
Oral administration of high doses did not produce deleterious cardiovascular effects in conscious dogs (25 mg/kg) and normotensive rats (25-50 mg/kg). Weak, transient dose-dependent effects on the pressor responses to exogenous NA and tyramine were seen in anaesthetized dogs; bupropion was approximately 10-fold weaker than imipramine in this regard. The compound essentially lacked sympathomimetic actions in dogs and cats.
10.3 Pharmacokinetics
Absorption
Bupropion has not been administered intravenously to humans; therefore, the absolute bioavailability of bupropion hydrochloride extended-release tablets in humans has not been determined. In rat and dog studies, the bioavailability of bupropion ranged from 5% to 20%. Following oral administration of bupropion hydrochloride sustained-release tablets to healthy volunteers, peak plasma concentrations of bupropion are achieved within 3 hours. In two single-dose (150 mg) studies the mean peak concentration (Cmax) values were 91 and 143 ng/mL. At steady state, the mean Cmax following a 150 mg dose every 12 hours was 136 ng/mL.
In a single-dose study, food increased the Cmax of bupropion by 11% and the extent of absorption as defined by area under the plasma concentration-time curve (AUC) by 17%. The mean time to peak concentration (Tmax) was prolonged by 1 hour. This effect was of no clinical significance.
Distribution
In vitro tests show that bupropion is 84% bound to human plasma proteins at concentrations up to 200mcg/mL. The extent of protein binding of hydroxybupropion is similar to that of bupropion, whereas the extent of protein binding of the threohydrobupropion metabolite is about half that seen with bupropion. The volume of distribution (Vss/F) estimated from a single 150 mg dose given to 17 subjects is 1,950 L (20% CV).
Metabolism
Bupropion is extensively metabolized in humans. There are three active metabolites: hydroxybupropion and the amino-alcohol isomers threohydrobupropion and erythrohydrobupropion, which are formed via hydroxylation of the tert-butyl group of bupropion and/or reduction of the carbonyl group. Oxidation of the bupropion side chain results in the formation of a glycine conjugate of meta-chlorobenzoic acid, which is then excreted as the major urinary metabolite. In preclinical tests used to predict antidepressant activity, it has been observed that hydroxybupropion is comparable in potency to bupropion, while the other metabolites are one half to one tenth as potent. This may be of clinical importance because the plasma concentrations of the metabolites are higher than those of bupropion.
In vitro results indicate that biotransformation of bupropion to hydroxybupropion is catalyzed primarily by CYP2B6, and to a much lesser extent by CYP1A2, 2A6, 2C9, 2E1 and 3A4 isozymes. Detectable levels of hydroxybupropion are not observed with CYP1A1 and CYP2D6 isozymes. Cytochrome P450 isoenzymes are not involved in the formation of threohyrobupropion. Following a single 150 mg dose of bupropion in humans, peak plasma concentrations of hydroxybupropion occur approximately 6 hours after administration. Peak plasma concentrations of hydroxybupropion are approximately 10 times the peak level of the parent drug at steady state. The AUC of hydroxybupropion at steady state is about 17-fold higher than that of bupropion. The times to peak concentrations for the erythrohydrobupropion and threohydrobupropion metabolites are similar to that of hydroxybupropion, and steady-state AUCs are 1.5 and 7 times that of bupropion, respectively.
Because bupropion is extensively metabolized, there is the potential for drug-drug interactions, particularly with those agents that are metabolized by the CYP2D6 isoenzyme. Although bupropion is not metabolized by CYP2D6, there is the potential for drug-drug interactions when bupropion is co-administered with drugs metabolized by this isoenzyme (see Drugs Metabolized by Cytochrome P450 (CYP2D6) and 9.4 Drug-Drug Interactions).
Elimination
In two single-dose (150 mg) studies the mean (±% CV) apparent clearance (Cl/F) of bupropion was 135 (±20%) and 209 L/hr (±21%). Following chronic dosing of 150 mg of bupropion hydrochloride sustained-release tablets every 12 hours for 14 days (n = 34), the mean Cl/F at steady state was 160 L/hr (±23%). The mean elimination half-life of bupropion (estimated from a series of studies) is approximately 21 hours. Estimates of the half-lives of the metabolites determined from a multiple-dose study were 20 hours (25%) for hydroxybupropion, 37 hours (35%) for threohydrobupropion, and 33 hours (30%) for erythrohydrobupropion. Steady-state plasma concentrations of bupropion and metabolites are reached within 5 and 8 days, respectively. Following oral administration of 200 mg of 14C-bupropion in humans, 87% and 10% of the radioactive dose were recovered in the urine and faeces, respectively. The fraction of the oral dose of bupropion excreted unchanged was only 0.5%. Bupropion and its metabolites exhibit linear kinetics following chronic administration of 150 to 300 mg/day.
Dose proportionality
A randomized, two-way, single-dose, crossover bioavailability study with 35 healthy adult male and female volunteers was conducted under fasting conditions to determine the dose proportionality of the two strengths of bupropion hydrochloride extended-release tablets (2x150 mg versus 1x300 mg). A summary of the pharmacokinetic parameters obtained from the study is provided in the following Table 6. Bupropion hydrochloride extended-release tablets 150 mg and 300 mg tablets are dose proportional with respect to blood levels.
Table 6: Bupropion Hydrochloride Extended-Release Tablet Dose Proportionality
Bupropion 2x150 mg versus 1 x 300 mg Arithmetic Mean (CV%) | ||
| Parameter | Bupropion hydrochloride extended-release tablets 2 x 150 mg | Bupropion hydrochloride extended-release tablets 1 x 300 mg |
| AUCT (ng.h/mL) | 1648.85 ± 475.34 | 1676.61 ± 474.09 |
| AUCI (ng.h/mL) | 1702.69 ± 489.30 | 1728.34 ± 478.43 |
| Cmax (ng/mL) | 150.11 ± 7.22 | 146.88 ± 47.61 |
| Tmax (h) | 4.99 ± 0.76 | 5.20 ± 0.88 |
| T1/2 (h) | 22.70 ± 7.42 | 21.84 ± 7.35 |
Special Populations and Conditions
Factors or conditions altering metabolic capacity (e.g., liver disease, congestive heart failure, age, concomitant medications, etc.) or elimination may be expected to influence the degree and extent of accumulation of the active metabolites of bupropion. The elimination of the major metabolites of bupropion may be affected by reduced renal or hepatic function because they are moderately polar compounds and are likely to undergo further metabolism or conjugation in the liver prior to urinary excretion.
- Pediatrics: Based on the data submitted and reviewed by Health Canada, the safety and efficacy of bupropion hydrochloride extended-release tablets in pediatric patients has not been established; therefore, Health Canada has not authorized an indication for pediatric use.
- Geriatrics: The effects of age on the pharmacokinetics of bupropion and its metabolites have not been fully characterized, but an exploration of steady state bupropion concentrations from several depression efficacy studies involving patients dosed in a range of 300 to 750 mg/day, on a three times a day schedule, revealed no relationship between age (18 to 83 years) and plasma concentration of bupropion. A single-dose pharmacokinetic study demonstrated that the disposition of bupropion and its metabolites in elderly subjects was similar to that of younger subjects. These data suggest there is no prominent effect of age on bupropion concentration: however, another single and multiple dose pharmacokinetic study, has suggested that the elderly are at increased risk for accumulation of bupropion and its metabolites (see 7.1.4 Geriatrics and Geriatrics or Debilitated Patients).
- Ethnic Origin: The influence of race (Asian, Black and Caucasian) on the pharmacokinetics of bupropion (bupropion hydrochloride immediate release tablets) was evaluated based on dose normalized data pooled from five healthy volunteer studies. A comparison of pharmacokinetic parameter values did not detect any important differences in race with respect to AUC (p = 0.5564) and Cmax (p = 0.8184).
- Hepatic Insufficiency: The effect of hepatic impairment on the pharmacokinetics of bupropion was characterized in two single-dose studies, one in subjects with alcoholic liver disease and one in subjects with mild to severe liver cirrhosis.
The first study involved 8 subjects with alcoholic liver disease, and 8 healthy matched controls. While mean AUC values were not significantly different, individual AUC values for both the parent drug bupropion and the primary metabolite hydroxybupropion were more variable in subjects with alcoholic liver disease and increased by approximately 50% over those of healthy volunteers. The mean half-life of the primary metabolite hydroxybupropion was significantly longer by approximately 40% in subjects with alcoholic liver disease than in healthy volunteers (32±14 hours versus 21±5 hours, respectively). For all other pharmacokinetic values, for both parent drug and metabolites, there were minimal differences between the two groups.
The second study involved 17 subjects with hepatic impairment (n = 9 mild/Grade A child-Pugh rating; n = 8 severe/Grade C Child-Pugh rating) and 8 healthy matched controls. In the severe group, the mean value for bupropion AUC was increased threefold over control values, with mean clearance decreased proportionately. Mean Cmax and plasma half-life were increased by approximately 70% and 40% respectively. For the primary metabolites, mean AUC was increased by approximately 30% - 50%, with mean clearance decreased proportionately. Mean Cmax was lower by approximately 30% to 70%, and mean plasma half-life increased threefold.
In the mild group, while mean values were not statistically increased from those of controls, the variability in the pharmacokinetic values was higher in the subjects with impairment; a sub-group of 1 to 3 subjects (dependent on pharmacokinetic parameter examined) showed individual values which were in the range of the severely impaired subjects. For the primary metabolites, the differences between groups in pharmacokinetic parameters were minimal.
In patients with hepatic impairment, treatment should be initiated at reduced dosage (see
Hepatic/Biliary/Pancreatic and Hepatic Impairment).
- Effect of Smoking: In a single dose study, there were no significant differences in the pharmacokinetics of bupropion or its major metabolites in smokers compared with non-smokers.
11 STORAGE, STABILITY AND DISPOSAL
Store at 15°C to 30°C.
Keep out of sight and reach of children
12 SPECIAL HANDLING INSTRUCTIONS
No special handling instructions are needed.
PART II: SCIENTIFIC INFORMATION
13 PHARMACEUTICAL INFORMATION
Drug Substance
Proper Name: Bupropion hydrochloride
Chemical Name: 1-(3-chlorophenyl)-2-[(1,1-dimethylethyl)amino]-1-propanone hydrochloride
Molecular Formula and Molecular Mass: C13H18ClNO.HCl 276.21 g/mol
Structural formula:
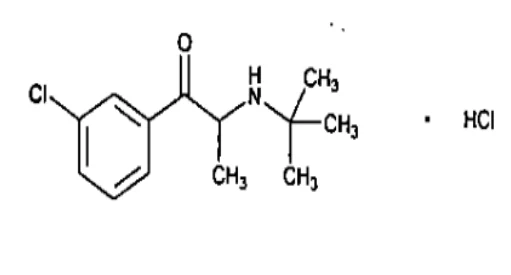
Physiochemical Properties:
Bupropion hydrochloride is a white powder. Soluble in water, in 0.1N hydrochloric acid, and in alcohol.
14 CLINICAL TRIALS
14.1 Clinical Trials by Indication
Major Depressive Disorder
Table 7 –Summary of Patient Demographics for Clinical Trials in Major Depressive Disorder
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean age (range) | Gender (M/F) | ||||||
| AK13 0926 | Bupropion hydrochloride extended-release tablets 300-450 mg/day (450 mg was taken in two divided doses -300 mg am. dose followed 8 hours later by 150 mg dose), oral 8-week treatment period | 135 | 18-65 | 59/76 | |||||||
escitalopram Placebo oral 8-week treatment period | 132 | 18-62 | 56/76 | ||||||||
| AK13 0927 | Bupropion hydrochloride extended-release tablets 300-450 mg/day (450 mg was taken in two divided doses -300 mg am. dose followed 8 hours later by 150 mg dose), po | 141 | 19-71 | 56/85 | |||||||
The treatment groups, as well as the total population (across all three studies), were comparable with respect to demographic characteristics. The majority of the subjects across the treatment groups were Female (61%), White (71%), with a mean age of 37 years. The treatment groups were also similar with respect to height, weight, and BMI.
Table 8 – Results of Studies AK130926, AK130927 and AK130931 in Major Depressive Disorder
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
Studies AK130926, AK130927 As studies AK130926 and 130927 were identical in design, analyses of pooled data from the two studies were performed. When all the efficacy variables are taken into consideration, pooled data from studies AK130926 and AK130927 shows a consistently greater efficacy for bupropion hydrochloride extended-release tablets group than placebo group, with regard to Major Depressive Disorder. Bupropion hydrochloride extended-release tablets group demonstrated superiority over placebo group with regard to HAMD, CGI, HAD, and MEI assessments at Week 8(LOCF and Observed) and at Week 4(LOCF).The bupropion hydrochloride extended-release tablets group demonstrated statistical superiority over placebo group in ITT population as well as in the target dose population (300mg/day). | ||
Escitalopram-10-20 mg/day, once-a-day Placebo oral 8 week treatment period | 141 | 19-73 | 53/88 |
| AK13 0931 | |||
| Multicentre parallel group, double-blind, randomised | |||
Bupropion hydrochloride extended-release tablets 300-450 mg/day (450 mg as a single dose or in divided doses-300 mg am. dose followed 8 hours later by 150 mg dose), oral 8-week treatment period | 135 | 20-68 | 46/89 |
Placebo oral 8-week treatment period | 139 | 19-69 | 43/96 |
Study AK130931 For the primary efficacy endpoint, subjects in bupropion hydrochloride extended-release tablets group exhibited significant improvement over placebo group for overall depressive symptoms measured as mean change from randomisation in IDS-SR (LOCF p=0.018). | Significant improvement was also demonstrated in total scores for IDS-C (LOCF p<0.001) and in the subscale of IDS-SR pertaining to pleasure, energy, and interest (LOCF p=0.007). | The mean change from randomisation in IDS-SR total score at Week 8 (Observed) for the bupropion hydrochloride extended-release tablets group was statistically significantly greater (bupropion hydrochloride extended-release tablets)mean=- 24.4 vs. placebo=-19.3, p=0.005) than that in placebo group. |
Prevention of Seasonal Major Depressive Episodes
Table 9 - Summary of Patient Demographics for Clinical Trials in Prevention of Seasonal Major Depressive Episodes
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean age (range) | Gender (M/F) | |||
| AK130930 | Multicentre, Randomized, double-blind | Bupropion hydrochloride extended-release tablets 150 – 300 mg/day oral 7 months treatment | 140 | 42.1 (19 – 71) | 35 / 105 | |||
Placebo oral 7 months treatment | 132 | 43.0 (22 – 68) | 37 / 95 | |||||
| AK130936 | Multicentre, Randomized, double-blind | Bupropion hydrochloride extended-release tablets 150 – 300 mg/day oral 7 months treatment | 156 | 41.8 (20 – 78) | 53 / 103 | |||
Placebo oral 7 months treatment | 150 | 42.7 (22 – 78) | 46 / 104 | |||||
| Study # | Trial Design | Dosage, Route of Administration and Duration | Study Subjects (n) | Mean age (range) | Gender (M/F) | |||
| 100006 | Multicentre, Randomized, double-blind | Bupropion hydrochloride extended-release tablets 150 – 300 mg/day oral 7 months treatment | 238 | 41.2 (19 – 69) | 74 / 164 | |||
Placebo oral 7 months treatment | 226 | 40.9 (18 –70) | 68 / 158 | |||||
The treatment groups, as well as the total population (across all three studies), were comparable with respect to demographic characteristics. The majority of the subjects across the treatment groups were Female ( 70%), with a mean age of 45 years.
Table 10 – Results of Studies AK130930 and AK130936 and AK 100006 in Prevention of
Seasonal Major Depressive Episodes
| Primary Endpoints | Associated value and statistical significance for Drug at specific dosages | Associated value and statistical significance for Placebo or active control |
| The efficacy of bupropion hydrochloride extended-release tablets for the prevention of seasonal major depressive episodes was established in 3 double-blind, placebo-controlled trials in adult outpatients with a history of major depressive disorder with an autumn- winter seasonal pattern (as defined by DSM-IV criteria). Treatment was initiated prior to the onset of symptoms in the autumn (September to November) and was discontinued following a 2- week taper that began the first week of spring (fourth week of March), resulting in treatment duration of approximately 4 to 6 months for the majority of patients. | At the start of the study, patients were randomized to receive placebo or bupropion hydrochloride extended-release tablets 150 mg once daily for 1 week, followed by up-titration to 300 mg once daily. Patients who were deemed by the investigator to be unlikely or unable to tolerate 300 mg once daily were allowed to remain on, or had their dose reduced to, 150 mg once daily. The mean bupropion hydrochloride extended-release tablets doses in the 3 studies ranged from 257 to 280 mg/day. | In these 3 trials, the percentage of patients who were depression-free at the end of treatment was significantly higher for bupropion hydrochloride extended-release tablets than for placebo: 81.4% vs 69.7%, 87.2% vs 78.7% and 84.0% vs 69.0% for Study 1, 2 and 3, respectively, with a depression-free rate for the 3 studies combined of 84.3% vs 72.0%. |
14.3 Comparative Bioavailability Studies
FASTING CONDITION:
A single dose of TARO-BUPROPION XL tablets 150 mg was administered to 28 healthy volunteers to evaluate the bioequivalence between reference Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 150 mg manufactured by Valeant Canada LP and TARO-BUPROPION XL tablets 150 mg [Sun Pharma Canada Inc.] formulations under fasting condition. The results from measured data in 24 subjects are summarised in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Bupropion (1 x 150 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means5 | 90% Confidence Interval |
AUC0-t (ng.hr/mL) | 838.9313 892.6764 (37.77) | 802.6331 838.7668 (31.00) | 104.1 | 92.2- 117.6 |
AUC0-∞ (ng.hr/mL) | 880.3102 933.6400 (38.96) | 845.8498 881.8153 (31.95) | 103.7 | 92.3- 116.4 |
Cmax (ng /mL) | 100.588 106.993 (38.61) | 81.834 85.890 (32.43) | 121.4 | 108.3 6 -136.26 |
Tmax3 (h) | 4.667 (3.000 – 7.500) | 4.667 (3.000 – 7.500) | ||
| T1/24 (h) | 17.0908 (34.11) | 17.6089 (34.38) | ||
1 TARO-BUPROPION 150 mg XL tablets (Sun Pharma Canada Inc.)
Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 150 mg (Valeant Canada LP, Canada) were purchased in Canada.
3 Expressed as Median (Range) only
4 Expressed as Arithmetic Mean (CV%) only
5 Calculation based on least squares estimate
6: For Information Purpose only.
FED CONDITION:
A single dose of TARO-BUPROPION XL tablets 150 mg was administered to 28 healthy volunteers to evaluate the bioequivalence between reference Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 150 mg manufactured by Valeant Canada LP and TARO-BUPROPION XL tablets 150 mg [Sun Pharma Canada Inc.] formulations under fed condition. The results from measured data in 25 subjects are summarised in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Bupropion (1 x 150 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means5 | 90% Confidence Interval |
AUC0-t (ng.hr/mL) | 822.4095 850.0794 (25.23) | 834.2225 857.3519 (24.02) | 98.7 | 93.7 - 103.4 |
AUC0-∞ (ng.hr/mL) | 859.1448 886.3394 (24.61) | 867.7158 891.0593 (23.68) | 98.8 | 94.0 - 103.9 |
Cmax (ng /mL) | 82.884 84.754 (21.62) | 84.495 87.220 (25.71) | 97.6 | 91.66- 104.16 |
Tmax3 (h) | 7.667 (4.500 – 10.500) | 5.500 (4.000 –10.000) | ||
| T1/24 (h) | 16.6914 (43.12) | 14.7486 (47.65) | ||
1TARO-BUPROPION 150 mg XL tablets (Sun Pharma Canada Inc.)
2 Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 150 mg (Valeant Canada LP, Canada) were purchased in Canada.
3 Expressed as Median (Range) only
4 Expressed as Arithmetic Mean (CV%) only
5 Calculation based on least squares estimate
6: For Information Purpose only.
FASTING CONDITION:
A single dose of TARO-BUPROPION XL tablets 300 mg was administered to 30 healthy volunteers to evaluate the bioequivalence between reference Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 300 mg manufactured by Valeant Canada LP and
TARO-BUPROPION XL tablets 300 mg [Sun Pharma Canada Inc.] formulations under fasting condition. The results from measured data in 28 subjects are summarised in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Bupropion (1 x 300 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means5 | 90% Confidence Interval |
AUC0-t (ng.hr/mL) | 1564.1391 1654.7283 (38.12) | 1530.5463 1623.7929 (38.55) | 102.2 | 91.4- 114.3 |
AUC0-∞ (ng.hr/mL) | 1613.5708 1701.4163 (36.68) | 1572.2998 1663.7447 (37.54) | 102.3 | 92.0 - 114.4 |
Cmax (ng /mL) | 168.538 180.751 (39.97) | 170.580 180.789 (37.22) | 98.8 | 88.3 6 -110.66 |
Tmax3 (h) | 5.667 (3.000 – 12.000) | 4.667 (3.500 – 8.000) | ||
| T1/24 (h) | 19.5682 (26.65) | 17.0433 (30.74) | ||
1 TARO-BUPROPION 150 mg XL tablets (Sun Pharma Canada Inc.)
2 Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 300 mg (Valeant Canada LP, Canada) were purchased in Canada.
3 Expressed as Median (Range) only
4 Expressed as Arithmetic Mean (CV%) only
5 Calculation based on least squares estimate
6: For Information Purpose only.
FED CONDITION:
A single dose of TARO-BUPROPION XL tablets 300 mg was administered to 30 healthy volunteers to evaluate the bioequivalence between reference Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 300 mg manufactured by Valeant Canada LP and TARO-BUPROPION XL tablets 300 mg [Sun Pharma Canada Inc.] formulations under fed condition. The results from measured data in 26 subjects are summarised in the following table.
SUMMARY TABLE OF THE COMPARATIVE BIOAVAILABILITY DATA
Bupropion (1 x 300 mg) From measured data Geometric Mean Arithmetic Mean (CV %) | ||||
|---|---|---|---|---|
| Parameter | Test1 | Reference2 | % Ratio of Geometric Means5 | 90% Confidence Interval |
AUC0-t (ng.hr/mL) | 1952.1541, 1982.4171 (18.03) | 2025.9801, 2057.5932 (18.40) | 96.8 | 91.7- 102.2 |
AUC0-∞ (ng.hr/mL) | 1999.8443, 2029.0140 (17.48) | 2072.9933, 2104.7871 (18.27) | 96.9 | 91.9- 102.2 |
Cmax (ng /mL) | 154.731, 162.407 (31.49) | 184.260, 188.683 (22.69) | 83.7 | 75.9 6 - 92.4 6 |
Tmax3 (h) | 9.509 (4.500 – 13.000) | 6.333 (4.000 – 11.000) | ||
| T1/24 (h) | 19.6476 (26.57) | 20.9706 (20.65) | ||
1 TARO-BUPROPION 150 mg XL tablets (Sun Pharma Canada Inc.)
2 Wellbutrin® XL (bupropion hydrochloride) Extended Release Tablets 300 mg (Valeant Canada LP, Canada) were purchased in Canada.
3 Expressed as Median (Range) only
4 Expressed as Arithmetic Mean (CV%) only
5 Calculation based on least squares estimate
6: For Information Purpose only.
15 MICROBIOLOGY
No microbiological information is required for this drug product.
16 NON-CLINICAL TOXICOLOGY
General Toxicology
Three acute toxicity studies (LD50) were carried out in mice and rats at doses ranging from 175 to 700 mg/kg. The LD50 ranged from 263 mg/kg in male Long-Evans rats to 636 mg/kg in female CD-1 mice. Clinical signs included convulsions, ataxia, loss of righting reflex, laboured breathing, prostration, salivation and ptosis.
Five repeated dose toxicity studies have been performed in the rat. In a 14-day oral toxicity study in rats, a reversible dose-related increase in absolute and relative liver weights (approximately 5-30%) was noted in males and females in all treated groups at termination of dosing. The doses used in this study were 0, 100, 200 and 300 mg/kg/day. These liver weight increases were related to microsomal enzyme production. No other treatment related changes were found. In a 90-day study, dose-related irritability and urinary incontinence was observed. A dose related increase in liver weight was noted. The dosage used was up to 450 mg/kg/day.
In a 55-week study in rats, a dose-related increase in the frequency of yellow staining of the fur around the anogenital region was observed. Other findings were dry brown material around the nose or mouth and moisture around the mouth, especially soon after dosing. No compound related effects on body weight, food consumption, haematology, biochemistry or urinalysis was observed. No compound related gross pathological findings were noted. Statistically significant increases in group mean liver and kidney weights across all treated groups and a slight increase in iron positive pigment in the spleens of males at 100 mg/kg/day were noted.
In repeat dose studies in dogs of up to fifty weeks, increased salivation, emesis and dry nose and/ or mouth were noted occasionally. Generally, body trembling and weakness were also seen at 150 mg/kg/day. Dose related frequency of occurrence of slight to moderate decrease in haemoglobin, haematocrit and total erythrocytes was noted at most intervals of analysis. Slight to moderate increase in SGPT and SGOT, alkaline phosphatase and BSP retention was noted in some dogs.
In rats receiving large doses of bupropion chronically, there was an increase in incidence of hepatic hyperplastic nodules and hepatocellular hypertrophy. In dogs receiving large doses of bupropion chronically, various histologic changes were seen in the liver, and laboratory tests suggesting mild hepatocellular injury were noted.
Increase in liver weights with associated hypertrophy in rats and dogs are commonly observed in lifetime bioassays with high doses of drugs which are inducers of microsomal enzymes. Such enzyme induction has been noted in animals but not in humans receiving bupropion. Moreover, available human data do not indicate liver toxicity associated with bupropion immediate release or sustained release.
Carcinogenicity
Lifetime carcinogenicity studies were performed in rats and mice at doses up to 300 and 150 mg/kg/day bupropion, respectively. These doses are approximately ten and two times the maximum recommended human dose (MRHD), respectively, on a mg/m2 basis. In the rat study there was an increase in nodular proliferative lesions of the liver at doses of 100 to 300 mg/kg/day; lower doses were not tested. The question of whether or not such lesions may be precursors of neoplasms of the liver is currently unresolved.
Similar liver lesions were not seen in the mouse study, and no increase in malignant tumours of the liver and other organs was seen in either study.
Bupropion produced a borderline positive response (2 to 3 times control mutation rate) in two of five strains in Ames bacterial mutagenicity test and an increase in chromosomal aberrations in one of three in vivo rat bone marrow cytogenetic studies. The relevance of these results in estimating the risk to human exposure to therapeutic doses is unknown.
Developmental Toxicology
A two-generation reproductive and fertility study in Long Evans rats receiving 100, 200, 300 mg/kg bupropion daily by gavage revealed no treatment or compound related effects observed on mating or fertility performance. No compound related effects were observed in reproductive ability, fertility, gross anatomic abnormalities, foetal deaths or pup survival and growth during lactation. In F1 generation females no compound related effects were observed on lactation, body weight at sacrifice, reproduction performance and post-mortem findings. Similarly, no compound related findings were observed in the clinical condition, reproductive performance or necropsy of the F1 males. In the F2 generation, no compound related effects were observed on the male:female ratio of pups, survival or bodyweight. No compound related effects were observed on necropsy.
Teratology studies have been performed at doses up to 450 mg/kg in rats, and at doses up to 150 mg/kg in rabbits (approximately 7 to 11 and 7 times the MRHD, respectively, on a mg/m2 basis), and have revealed no evidence of harm to the fetus due to bupropion.
17 SUPPORTING PRODUCT MONOGRAPHS
- 1. PrWellbutrin® XL (Bupropion Hydrochloride Extended-Release Tablets, 150 mg and 300 mg), Submission Control No. 287467, Product Monograph, Bausch Health, Canada Inc., Dec 16, 2024.