


Product Monograph - Teva-Tryptophan
ACTION AND CLINICAL PHARMACOLOGY
The rationale for the use of L-tryptophan in affective disorders is based on clinical findings more than 20 years ago, that L-tryptophan increases 5-HT (serotonin) synthesis in the central nervous system of humans. It has been demonstrated in clinical trials that oral ingestion of L-tryptophan in humans caused a significant increase in the level of the serotonin metabolite, 5-hydroxyindoleacetic acid (5-HIAA), in the lumbar cerebrospinal fluid, indicating an increased turnover of serotonin in the CNS.
L-tryptophan is one of the eight essential amino acids. The minimum daily requirements are said to be 0.25 g for males and 0.15 g for females. It is present in the hydrolysates of most proteins, the average western diet containing between 1 and 3 grams per day. There are two major metabolic pathways for L-tryptophan, the first to serotonin, the second to nicotinic acid. Approximately 98% of dietary L-tryptophan is metabolized into nicotinic acid and only a very small amount is being metabolized to serotonin via the intermediary stage of 5-hydroxy-tryptophan (5-HTP). Tryptophan hydroxylase, the enzyme responsible for this step, is the rate-limiting enzyme for serotonin production and is normally only about half-saturated. Central nervous system serotonin is metabolized by monoamine oxidase to 5-HIAA.
INDICATIONS AND CLINICAL USE
L-tryptophan is used as a valuable adjunct to antidepressant drug treatment in the management of patients suffering from depressive disorders (bipolar affective disorders). An adjunctive effect has been observed in some case when L-tryptophan is given in combination with lithium in bipolar patients with mania or depression for whom lithium alone or in combination with neuroleptics or tricyclics has been shown little or no effect. Clinical observations suggest the possibility that the combination of lithium and L-tryptophan may reduce the need for the higher, more toxic doses of lithium necessary to control acute mania.
CONTRAINDICATIONS
L-tryptophan is contraindicated in patients with known sensitivity to L-tryptophan or any other compound in the formulation.
WARNINGS
Monoamine Oxidase Inhibitors (MAOIs): L-tryptophan is not recommended in patients taking monoamine oxidase inhibitors (MAOIs including linezolide, methylene blue) or within 14 days of such therapy. The combination of MAOIs and tryptophan has been reported to cause behaviour and neurologic syndromes including disorientation, confusion, amnesia, delirium, agitation, hypomanic signs, ataxia, myoclonus, hyperreflexia, shivering, ocular oscillations and Babinski signs (see DRUG INTERACTIONS).
Serotonin Syndrome: There have been rare reports of serotonin syndrome with the concomitant use of L-tryptophan and serotonergic drugs. Caution is advise particularly during treatment initiation and dose increases when prescribing TEVA-TRYPTOPHAN with serotonergic drugs such as selective serotonin re-uptake inhibitor (SSRI) or serotonin norepinephrine re-uptake inhibitor (SNRI) products, as well as with tricyclic antidepressants (TCAs), and other serotonergic drugs (e.g. lithium, triptans and MAOIs). Treatment should be discontinued if patients develop a combination of symptoms possibly including hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, mental status changes including confusion, irritability, extreme agitation progressing to delirium and coma, and supportive symptomatic treatment should be initiated (see DRUG INTERACTIONS).
Allergic Reactions: There have been reports of hypersensitivity reactions (myalgia, oedema, pruritus, rash, urticaria and wheezing) with the use of L-tryptophan. Patients should be instructed to see their doctor if they develop any of these signs or symptoms.
L-tryptophan should not be given to patients suffering from the following conditions or should be prescribed only under close supervision:
Bladder Cancer: To minimize the risk of bladder cancer, it may be recommended to give vitamin B6 supplements if the L-tryptophan doses are many times in excess of those consumed normally in dietary protein. An increased incidence rate of bladder cancer has been observed in experimental animals after implantation of pellets containing any of the seven tryptophan metabolites formed by tryptophan pyrrolase. Active metabolites included kynurenine, 3-hydroxykynurenine, 3-hydroxyanthranillic acid, and xanthurenic acid, but not tryptophan itself. Vitamin B6 has been reported to correct the metabolism of L-tryptophan and to reduce the metabolites to normal levels. A large study carried out by the National Cancer Institute did not find L-tryptophan to produce cancer in either rats or mice. Elevated levels of L-tryptophan metabolites in the urine have been reported both in bladder cancer patients relative to controls, in patients who had a recurrence of cancer relative to those who did not and in patients taking oral contraceptives or hormones.
Diabetes mellitus: Xanthurenic acid, which is increased on L-tryptophan loading, has a diabetogenic action in animals, possibly due to its ability to bind insulin, suggesting caution in the use of tryptophan in patients with a family history of diabetes.
Achlorhydria/Malabsorption: In ruminants, oral L-tryptophan caused pulmonary edema and emphysema, mediated by bacterial conversion of L-tryptophan to skatole (3-methylindole). This is not normally of concern in humans except where bacteria exist high in the gastrointestinal tract due to conditions such as achlorhydria, or where L-tryptophan reaches the bacterial populations lower in the gastrointestinal tract due to malabsorption.
Cataract Formation: Animal data suggest that photooxidation of L-tryptophan and some of its metabolites, such as kynurenine, may be involved in cataract formation. Although there is no evidence that this occurs in humans, L-tryptophan administration is likely to raise lenticular tryptophan and kynurenine concentrations, and this might make subjects more susceptible to cataract formation, particularly if exposed to ultraviolet light.
PRECAUTIONS
Neurologic: Patients should be instructed not to drive, use machinery, or do any activity that requires alertness until they are sure they are can perform such activities safely.
DRUG INTERACTIONS
Drug interactions between tryptophan and other CNS affecting drugs have been reported. A higher occurrence of side effects was reported when tryptophan was given in combination with monoamino-oxidase inhibitors (MAOI). The most common side effects caused by this drug combination were dizziness, nausea and headache. At a dosage of 20-50 mg/kg tryptophan in addition to MAOI, the following side effects have been reported: ethanol-like intoxication, drowsiness, hyperreflexia and clonus. Single case reports of adverse reactions to the drug combination include hypomanic behavior, ocular oscillation, ataxia, and myoclonus. Some of these reactions resemble the
"serotonin syndrome" seen in experimental animals, which consists of tremor, hypertonus, myoclonus, and hyperactivity. These symptoms disappear soon after cessation of tryptophan and no detrimental long-term effects have been reported.
When tryptophan was given in combination with fluoxetine, the following side effects have been reported, but disappeared as soon as the medication was discontinued. Neither drug alone caused similar side-effects: agitation, restlessness, poor concentration, nausea, diarrhea, and worsening of obsessive-compulsive disorder.
Patients taking high doses of L-tryptophan should not be protein deprived since an amino acid imbalance can ensue.
ADVERSE REACTIONS
L-tryptophan, in doses below 5 g/day may cause dry mouth and drowsiness. In higher doses (9-12 g/day) nausea, anorexia, dizziness and headache have been reported.
Side effects disappear when medication is continued and in most cases only a light dizziness may persist.
Sexual disinhibition has been reported in some patients with emotional disorders.
L-tryptophan, when given with lithium, might increase some side effects associated with lithium therapy by potentiating the lithium effect (nausea, vomiting, dermatological eruptions, psoriasis, alopecia).
SYMPTOMS AND TREATMENT OF OVERDOSAGE
According to the toxicity described, symptoms of overdosage would include vomiting and might include serotonin syndrome symptoms. Treatment of overdosage would be symptomatic with close monitoring and support of vital systems as necessary.
| For management of a suspected drug overdose, contact your regional Poison Control Centre. |
DOSAGE AND ADMINISTRATION
Clinical reports on the use of L-tryptophan as an adjunct in the management of affective disorders have indicated the dose of 8-12 g/day to be the most effective one. Lower doses have been reported to be effective in combination with other antidepressants. Some patients may not tolerate 12 g/day but might still benefit from doses reduced to 8 g/day.
The treatment might be initiated with 12 g per day of L-tryptophan, given in 3-4 equally divided doses. Administration with meals or snacks is recommended to reduce the incidence of nausea. The dose and frequency of administration may have to be adjusted to the patients need and tolerance.
Special Populations and Conditions
A small number of bipolar patients are particularly sensitive to L-tryptophan and will not tolerated higher doses than 1 or 2 g/day. Patients on concomitant medication should be monitored for possible reduction of the concomitant medication since L-tryptophan may enhance their efficacy.
If L-tryptophan is used in the acute treatment of mania in conjunction with lithium, it will potentiate some of the side effects associated with lithium, such as nausea and vomiting. Thus, often it will be necessary to decrease the lithium dosage especially when it is given in doses above 900-1200 mg/day. In manic-depressive illness chronically treated with lithium, the lithium dose may need to be decreased when L-tryptophan is added because of increased side effects. In these patients, L-tryptophan tends to produce an increase in lithium concentrations, thus it is important to monitor the lithium concentration closely for at least two weeks after the addition of L-tryptophan.
With some of the more sedative neuroleptics and antidepressants, if L-tryptophan is added, an increased incidence of sedation may occur.
PHARMACEUTICAL INFORMATION
Drug Substance: L-tryptophan, USP
Chemical Name: L-2-Amino-3-(indol-3-yl) propionic acid
Structural Formula:
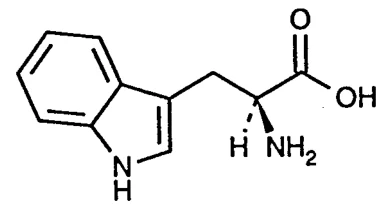 |
Molecular Formula: C11H12N202
Molecular Weight: 204.23
Description: White to slightly yellowish-white crystals or crystalline powder with a slightly bitter taste. It is soluble in 11.4 g in 1 L of water, slightly soluble in alcohol; practically insoluble in chloroform and ether; soluble in hot alcohol and solutions of dilute acids and alkali hydroxides. A 1% solution in water has a pH of 5.5 to 7.0.
Composition:
Capsules 500 mg: * L-tryptophan
* magnesium stearate
* talc
Tablets 500 mg * L-tryptophan
and 1 g: * calcium phosphate
* croscarmellose sodium
* magnesium stearate
* methylcellulose
* wax solution (white wax, carnauba wax)
* opaspray white
* film coating base solution (includes: acetylated monoglyceride, hydroxypropyl methylcellulose, povidone, titanium dioxide)
Storage
Recommendation: Store at controlled room temperature (15 - 30°C). Protect from heat and light.
AVAILABILITY OF DOSAGE FORMS
TEVA-TRYPTOPHAN 500 mg capsules: Each opaque white, hard gelatin capsule, size No. 00, branded "ALTI500" on cap and body contains: 500 mg of L-tryptophan, USP. Bottles of 100's and 250’s.
TEVA-TRYPTOPHAN 500 mg tablets: Each white, oval-shaped, film-coated tablet, embossed with "ALTIMED" on one side and with "500 mg" on the other side contains: 500 mg of L-tryptophan, USP. Bottles of 100's and 250’s.
TEVA-TRYPTOPHAN 1 g tablets: Each white, oval-shaped, film-coated tablet, embossed with "ALTI-TRYP" on top and "1g" underneath contains: 1 g of L-tryptophan, USP. Bottles of 100's and 250’s.
INFORMATION TO THE CONSUMER
For better results, TEVA-TRYPTOPHAN should be taken with a protein-low, carbohydrate-rich snack or meal.
TOXICOLOGY
In animals, the toxicity of parenterally administered tryptophan and other amino acids is attributed to ammonia poisoning. In rabbits, it causes histopathological changes in the kidney tubules, and large amounts given in conjunction with a low-protein diet cause death within a few days. It provokes a severe hyperglycemia which in the case of the l-isomer is not sustained since the animals die in a hypoglycemic state. L-tryptophan in toxic doses also causes marked glycosuria and loss of glycogen from skeletal muscle and liver. Some L-tryptophan metabolites cause experimental lymphomas or leukemias. The LD50 for L-tryptophan in the rat is 1.6 g/kg.
Carcinogenicity of L-tryptophan has been reviewed based on early findings relating bladder tumors in rats to aromatic amines and L-tryptophan. Experiments designed to provoke urinary bladder tumors by oral or subcutaneous administration of L-tryptophan or its metabolites, have generally given negative results. Tests performed on behalf of the National Cancer Institute (Bethesda, MD), using male and female rats and mice given large supplements of L-tryptophan for prolonged periods did not show a statistically significant occurrence of neoplasms as compared to controls. Under the bioassay, L-tryptophan was not carcinogenic for the strains of animals used. L-tryptophan and its tested metabolites have not exhibited intrinsic carcinogenic action. L-tryptophan has, however, been reported to promote or inhibit the carcinogenic action of a variety of known carcinogens.
L-tryptophan has been shown to cause hyperglycemia in rat and man, to inhibit gluconeogenesis in rat and man and to promote lipogenesis both in the fasted rat and the fed animal. Patients with scleroderma may exhibit abnormal L-tryptophan metabolism and studies have been carried out in an attempt to reveal a possible relationship between tryptophan and scleroderma. Serotonin given subcutaneously in a high dose for 30 days or more to rats was found to result in a scleroderma-like lesion. It is conceivable that the appearance of a sclerodermatous lesion can be initiated by different factors, among them a high level of kynurenine or metabolites of that amino acid, or of serotonin.
REFERENCES
- 1. Beitman B.D., Dunner D.L. L-tryptophan in the Maintenance Treatment of Bipolar II Manic-Depressive Illness. Am J Psychiatry 1982;139:1498-1499.
- 2. Boman B. L-tryptophan: A Rational Anti-Depressant and a Natural Hypnotic? Australian and New Zealand Journal of Psychiatry 1988;22:84-97.
- 3. Brewerton T.D., Reus V.I. Lithium Carbonate and L-tryptophan in the Treatment of Bipolar and Schizoaffective Disorders. Am J Psychiatry 1983;140:757-760.
- 4. Bryan G.T. The Role of Urinary Tryptophan Metabolites in the Etiology of Bladder Cancer. The American Journal of Clinical Nutrition 1971;24:841-847.
- 5. Chouinard G. Tryptophan and its Role in the Step-Care Approach to the Treatment of Affective Disorders. The Canadian Review of Affective Disorders 1991;1(2):1-8.
- 6. Chouinard G., Jones B.D., Young S.N. and Annable L. Potentiation of Lithium by Tryptophan in a Patient with Bipolar Illness. Am J Psychiatry 1979;136:719-720.
- 7. Chouinard G. and Annable L. A Controlled Clinical Trial of L-tryptophan in Acute Mania. Biol Psychiatry 1985;20:546-557.
- 8. Domino E.F. Pharmacokinetics of Oral Tryptophan in Drug-Free Psychiatric Patients. In: Gottschalk L.A., Merlis S., eds. Pharmacokinetics of Psychoactive Drugs. New York Spectrum Publications 1976;117-126.
- 9. Hedaya R.J. Pharmacokinetic Factors in the Clinical Use of Tryptophan. J Clin Psychopharmacol 1984;4(6):347-348.
- 10. Kennedy S.H., Bradwejn J., Joffe R.T. and Kusalic M. Practical Issues in Managing Bipolar Depression. Int Clin Psychopharmacology 1991;6:53-72.
- 11. Lowry F. Tryptophan might bolster Lithium's effect. The Medical Post, May 14, 1985;36.
- 12. Moller S.E., Kirk L. and Fremming K.H. Plasma Amino Acids as an Index for Subgroups in Manic Depressive Psychosis: Correlation to Effect of Tryptophan. Psychopharmacology 1976;49:205-213.
- 13. Price J.M., Thornton M.J. and Mueller L.M. Tryptophan Metabolism in Women Using Steroid Hormones for Ovulation Control. The American Journal of Clinical Nutrition 1967;20:452-456.
- 14.
Primeau F. and Chouinard G. Step-Care Approach in the Treatment of Bipolar
- Affective Illness. (unpublished)
- 15. Young S.N. The Clinical Psychopharmacology of Tryptophan. Nutrition and the Brain 1986;7:49-88.