


Product Monograph - Ratio-Minocycline
INDICATIONS AND CLINICAL USE
ratio-MINOCYCLINE (minocycline hydrochloride) may be indicated for the treatment of the following infections due to susceptible strains of the designated organisms:
Gall bladder infections caused by Escherichia coli.
Urinary tract infections: cystitis, gonorrhea, pyelonephritis caused by Escherichia coli,
Proteus species, Klebsiella species, Enterobacter aerogenes, Neisseria gonorrhea.
When penicillin is contraindicated, ratio-MINOCYCLINE may be employed as an alternative drug in the treatment of anal and pharyngeal gonorrhea and syphilis.
Skin and soft tissue infections: abscess, cellulitis, furunculosis, impetigo and pyoderma caused by: Staphylococcus epidermidis, Staphylococcus aureus, Streptococcus pyogenes, Proteus species, Escherichia coli. Although tetracyclines are not the drugs of choice in any staphylococcal or streptococcal infection, ratio-MINOCYCLINE could be useful in circumstances where these organisms are shown to be resistant to other agents but sensitive to ratio-MINOCYCLINE. Bacterial evaluation of clinical cases involving
Proteus suggests a relatively lower success rate may be expected where these organisms are concerned.
Respiratory tract infections: bronchitis, pharyngitis, pneumonia, bronchopneumonia, sinusitis and tonsillitis caused by: Haemophilus influenzae, Klebsiella species,
Enterobacter species. Tetracyclines should not be prescribed for acute throat infections.
CONTRAINDICATIONS
History of hypersensitivity to ratio-MINOCYCLINE (minocycline hydrochloride) or any other tetracycline.
WARNINGS
Rarely, anaphylactic/anaphylactoid reactions including shock and fatalities have been associated with the administration of minocycline hydrochloride.
Gastrointestinal
Clostridium difficile-associated disease
Clostridium difficile-associated disease (CDAD) has been reported with the use of many antibacterial agents, including minocycline (see ADVERSE REACTIONS). CDAD may
range in severity from mild diarrhea to fatal colitis. It is important to consider this diagnosis in patients who present with diarrhea or symptoms of colitis, pseudomembranous colitis, toxic megacolon, or perforation of the colon subsequent to the administration of any antibacterial agent. CDAD has been reported to occur more than 2 months after the administration of antibacterial agents.
Treatment with antibacterial agents may alter the normal flora of the colon and may permit overgrowth of Clostridium difficile. C. difficile produces toxins A and B, which contribute to the development of CDAD. CDAD may cause significant morbidity and mortality. CDAD can be refractory, to antimicrobial therapy.
If the diagnosis of CDAD is suspected or confirmed, appropriate therapeutic measures should be initiated. Mild cases of CDAD usually respond to discontinuation of antibacterial agents not directed against Clostridium difficile. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation, and treatment with an antibacterial agent clinically effective against Clostridium difficile. Surgical evaluation should be instituted as clinically indicated since surgical intervention may be required in certain severe cases.
Newborns, Infants and Children:
The use of tetracyclines, including ratio-MINOCYCLINE (minocycline hydrochloride), during tooth development (last half of pregnancy, infancy and childhood under the age of thirteen years) has been shown to cause permanent tooth discolouration (yellow-grey-brown). This is more common during long-term use, but has been observed following short-term courses. Enamel hypoplasia has also been reported. All tetracyclines, including ratio-MINOCYCLINE, administered during the last trimester form a stable calcium complex throughout the human fetal skeleton. A decrease in the fibula growth rate has been observed in premature human infants given oral tetracycline in doses of 25
mg/kg every 6 hours. This appeared to be reversible when the drug was discontinued.
Minocycline should not be used in such patients unless other drugs are ineffective or are contraindicated.
Congenital anomalies including limb reductions have been reported in post-marketing experience.
Pregnancy and Lactation:
Tetracyclines, including ratio-MINOCYCLINE, are not recommended during pregnancy and lactation because of possible adverse effects on developing bones and teeth of the fetus and neonate. Results of animal studies indicate that tetracyclines cross the placenta, are found in fetal tissues and can have toxic effects on the developing fetus (often related to retardation of skeletal development). If minocycline hydrochloride is used during pregnancy or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
Evidence of embryotoxicity has also been noted in animals treated early in pregnancy. The safety of ratio-MINOCYCLINE for use during pregnancy has not been established.
Tetracyclines, including ratio-MINOCYCLINE, are excreted in the milk of lactating women;
therefore, a decision should be made whether to discontinue breast-feeding or to discontinue minocycline.
It is advisable to avoid giving ratio-MINOCYCLINE in conjunction with penicillin since some bacteriostatic drugs may interfere with the bactericidal action of penicillin.
ratio-MINOCYCLINE should not be used for the treatment of streptococcal diseases unless the organism is demonstrated to be sensitive, since most streptococci have been found to be resistant to tetracycline drugs. If it is deemed necessary that infection due to
Group A beta-hemolytic streptococci be treated with ratio-MINOCYCLINE, then such treatment should be continued for at least ten days.
In the presence of significant renal impairment, usual oral doses may lead to excessive systemic accumulations of ratio-MINOCYCLINE and possible liver toxicity. Under such conditions, lower than usual doses may be indicated. After initial therapy, and if therapy is prolonged, serum level determinations of the drug are advisable.
The anti-anabolic action of tetracyclines can also produce dose-related increases in BUN, consequently, in patients with significant renal impairment, elevated serum ratio-
MINOCYCLINE levels can lead to azotemia, hypophosphatemia and acidosis.
Renal failure, including interstitial nephritis, has been reported rarely.
ratio-MINOCYCLINE is capable of aggravating the symptoms associated with lupus erythematosus. Therefore, caution should be taken when administering the drug to patients with this disease.
ratio-MINOCYCLINE has been shown to depress plasma prothrombin activity. Therefore, patients who are on anticoagulant therapy should be monitored regularly and may require downward adjustment of their anticoagulant dosage. Interference with vitamin K synthesis by micro-organisms in the gut has been reported.
Cross-sensitization among the various tetracyclines is extremely common.
Pigmentation of skin, thyroid, bone and teeth have been reported occasionally in persons receiving ratio-MINOCYCLINE usually for extended periods of time. The pigmentation may be irreversible.
Reduced efficacy and increased incidence of breakthrough bleeding has been suggested with concomitant use of tetracycline and oral contraceptive preparations.
PRECAUTIONS
The administration of ratio-MINOCYCLINE (minocycline hydrochloride) to children under
13 years of age is not recommended.
Very rare, serious events have occurred with minocycline hydrochloride including Stevens-
Johnson Syndrome and toxic epidermal necrolysis. Minocycline hydrochloride should be discontinued if either of these serious skin reactions is suspected.
Bulging fontanelles have been reported in young infants following full therapeutic dosage of tetracyclines including ratio-MINOCYCLINE. Pseudotumor cerebri (benign intracranial hypertension) has been reported in adults. (See Adverse Reactions section). The usual clinical manifestations are headache and blurred vision. While both of these conditions and related symptoms usually resolve after discontinuation of the tetracycline, the possibility of permanent sequelae exists.
Patients should be warned to avoid exposure to direct sunlight and/or ultraviolet light while under treatment with ratio-MINOCYCLINE or other tetracycline drugs, and treatment should be discontinued at the first evidence of skin erythema or discomfort.
Photosensitivity manifested by an exaggerated sunburn reaction has been observed in
some individuals taking tetracyclines. Studies to date indicate that photosensitivity is rarely reported with ratio-MINOCYCLINE.
Patients treated with ratio-MINOCYCLINE may suffer from headaches, light-headedness, dizziness or vertigo. Decreased hearing has been rarely reported in patients on minocycline hydrochloride. Administration of ratio-MINOCYCLINE in excess of the recommended dosage can increase the frequency and severity of these CNS symptoms.
Patients should be cautioned about driving vehicles or using hazardous machinery while on ratio-MINOCYCLINE therapy. These symptoms may disappear during therapy and usually disappear rapidly when the drug is discontinued.
As with other antibiotics, ratio-MINOCYCLINE therapy may result in overgrowth of nonsusceptible organisms (including fungi). If superinfection occurs, ratio-MINOCYCLINE should be discontinued and appropriate therapy instituted.
The development of cross-resistance to many antibiotics can develop rapidly in several species of micro-organisms. The clinician should bear this in mind if therapy with ratio-
MINOCYCLINE is not achieving expected results.
The frequency of resistance to ratio-MINOCYCLINE in hemolytic streptococci is highest in strains from infections of the ear, wounds and skin. Culture and sensitivity studies should be performed whenever feasible and routinely in suspected streptococcal infections. Since sensitivity reactions are more likely to occur in persons with a history of allergy, asthma, hay fever, or urticaria, ratio-MINOCYCLINE should be used with caution in such individuals.
Before treating patients with gonorrhea, a darkfield examination should be made from any lesion suggestive of concurrent syphilis. Serological tests for syphilis should be repeated monthly for at least 4 months.
Hepatotoxicity has been reported with minocycline hydrochloride; therefore, minocycline hydrochloride should be used with caution in patients with hepatic dysfunction and in conjunction with alcohol or other hepatotoxic drugs.
Periodic laboratory evaluation of organ systems, including hematopoietic, renal and hepatic studies, should be performed.
ratio-MINOCYCLINE has been shown to depress plasma prothrombin activity. Therefore, patients who are on anticoagulant therapy should be monitored regularly and may require downward adjustment of their anticoagulant dosage. Interference with vitamin K synthesis by micro-organisms in the gut has been reported.
Antacids containing aluminum, calcium or magnesium and oral iron preparations impair absorption and should not be given to patients taking oral ratio-MINOCYCLINE.
Food and/or milk reduce the absorption of tetracycline. ratio-MINOCYCLINE is not affected to the same extent.
In a study by Leyden, the absorption of a single 100 mg dose of minocycline was inhibited by the ingestion of solid food by 13% (as measured by a reduction in mean serum concentration), and the absorption of a single 250 mg dose of tetracycline was inhibited by 46% when that antibiotic was administered with solid food. When administered with milk, the mean serum concentration of minocycline was reduced by
27% and that of tetracycline, by 65%. The clinical significance of such declines in serum levels is not known.
The concurrent use of tetracyclines with oral contraceptives may render oral contraceptives less effective.
Administration of isotretinoin or other systemic retinoids or retinol should be avoided shortly before, during, and shortly after minocycline therapy. Each of these agents used alone has been associated with pseudotumor cerebri.
Increased risk of ergotism when ergot alkaloids or their derivatives are given with tetracyclines.
The following syndromes have been reported. In some cases involving these syndromes, death has been reported. As with other serious adverse reactions, if any of these syndromes are recognized, the drug should be discontinued immediately:
- Hypersensitivity syndrome consisting of cutaneous reaction (such as rash or exfoliative dermatitis), eosinophilia, and one or more of the following: hepatitis, pneumonitis, nephritis, myocarditis, pericarditis. Fever and lymphadenopathy may be present.
- Lupus-like syndrome consisting of positive antinuclear antibody; arthralgia, arthritis, joint stiffness, or joint swelling; and one or more of the following: fever, myalgia, hepatitis, rash, vasculitis.
- Serum sickness-like syndrome consisting of fever; urticaria or rash; and arthralgia, arthritis, joint stiffness, or joint swelling. Eosinophilia may be present.
ADVERSE REACTIONS
The following adverse reactions have been reported with the tetracycline analogues including ratio-MINOCYCLINE (minocycline hydrochloride):
(a) Central Nervous System: increased intracranial pressure, light-headedness, dizziness or vertigo and, rarely, fainting spells have been reported with a variable but overall incidence of approximately 7% in patients treated with ratio-MINOCYCLINE. These symptoms usually disappear rapidly when the drug is discontinued. Impaired hearing, tinnitus, headache, convulsions, sedation, hypesthesia or paresthesia have also been reported.
(b) Gastrointestinal System: anorexia, nausea, vomiting, diarrhea, stomatitis, glossitis, enterocolitis, pancreatitis, pruritis ani, constipation, dysphagia, inflammatory lesions (with monilial overgrowth) in the anogenital region, increases in liver enzymes, and rarely hepatitis and acute liver failure have been reported. Rare instances of esophagitis and esophageal ulcerations have been reported in patients taking the tetracycline-class antibiotics in capsule and tablet form. Most of these patients took the medication immediately before going to bed. Very rare incidence of pseudomembranous colitis has been reported.
(c) Teeth and Bone: dental staining (yellow-gray-brown) has been reported in children of mothers given tetracyclines, including ratio-MINOCYCLINE, during the latter half of pregnancy, and in children given the drug during the neonatal period, infancy and childhood to age of 13 years. Enamel hypoplasia has also been reported. Discolouration of bones and teeth has been documented to occur rarely in adolescents and adults upon extended
treatment with ratio-MINOCYCLINE. The effects may be irreversible. At present, the mechanism of staining, although not completely elucidated, appears to be mediated by the formation of a stable iron complex. Very rarely arthritis, joint stiffness and joint swelling have been reported.
(d) Renal: rise in BUN has been reported and is apparently dose-related.
Increased excretion of nitrogen and sodium has also been reported. Acute renal failure, including interstitial nephritis has been reported rarely.
(e) Skin: maculopapular and erythematous rashes. Rarely reported - alopecia, fixed drug eruption, photosensitivity, pruritus, rash, urticaria, onycholysis, discolouration of the nails, tongue, gum and lip, pigmentation of the skin and mucous membrane, erythema multiforme, erythema nodosum. Lesions occurring on the glans penis have caused balanitis. Very rare, serious events have occurred with minocycline hydrochloride including angioedema, exfoliative dermatitis, hyperpigmentation of nails, Stevens-Johnson
Syndrome, vasculitis and toxic epidermal necrolysis. Minocycline hydrochloride should be discontinued if either of these serious skin
Hypersensitivity reactions: urticaria, angioneurotic edema, polyarthralgia, anaphylaxis/anaphylactoid reactions (including shocks and fatalities), hypersensitivity, anaphylactoid purpura, pericarditis and exacerbation of systemic lupus erythematosus. Myalgia and Myocarditis have also been rarely reported.
(f) Pseudotumor cerebri (benign intracranial hypertension) in adults has been associated with the use of tetracyclines. The usual clinical manifestations are headache and blurred vision. Bulging fontanelles have been associated with the use of tetracyclines in infants. While both of these conditions and
related symptoms usually resolve soon after discontinuation of the tetracycline, the possibility for permanent sequelae exists.
(g) Respiratory: rarely – cough and dyspnea, very rarely – bronchospasm, exacerbation of asthma and pulmonary eosinophilia and undetermined frequency of pneumonitis have been reported.
(h) Other: fever, elevated liver enzymes including SGOT or SGPT values, hepatic cholestasis, hepatic failure (including fatalities) hyperbilirubinemia, jaundice, autoimmune hepatitis, hemolytic anemia, leukopenia, neutropenia, thrombocytopenia, eosinophilia and pancytopenia and agranulocytosis.
When given over prolonged periods, ratio-MINOCYCLINE, like other tetracyclines, has been reported to produce brown-black microscopic discolouration of the thyroid gland. Abnormalities of thyroid function have not been shown to date. If adverse reactions or idiosyncrasy occur, the administration of ratio-MINOCYCLINE should be discontinued and appropriate alternate therapy instituted. Very rare incidence of oral and anogenital candidiasis and vulvovaginitis have also been reported. Very rarely - discolouration of secretions have been reported.
SYMPTOMS AND TREATMENT OF OVERDOSAGE
Symptoms and Signs:
Dizziness, nausea, vomiting, abdominal pain, intestinal hemorrhage, hypotension, lethargy, coma, acidosis, azotemia without a concomitant rise in creatinine.
Treatment:
Specific antidote: None. General antidotes: Antacids (e.g., calcium carbonate or lactate, milk of magnesia, aluminium hydroxide) which form relatively insoluble complexes with ratio-MINOCYCLINE. (Calcium Solution 5%: 50 g calcium carbonate or lactate dissolved in 1000 mL water, yields a 5% solution). Gastric lavage, if necessary.
For management of a suspected drug overdose, CPhA recommends that you contact your regional Poison Control Centre. See the CPS Directory section for a list of Poison Control
Centres.
DOSAGE AND ADMINISTRATION
Children 13 Years of Age or Older:
The usual dosage of ratio-MINOCYCLINE (minocycline hydrochloride) is 4 mg/kg initially followed by 2 mg/kg every 12 hours. Tetracyclines are not recommended in children under
13 years of age (see WARNINGS).
Adults:
The usual oral dosage of ratio-MINOCYCLINE (minocycline hydrochloride) is 100 mg or
200 mg initially, followed by 100 mg every 12 hours. Alternatively, if more frequent doses are preferred, two or four 50 mg doses may be given initially, followed by one 50 mg dose every 6 hours. Therapy should be continued for 1 or 2 days beyond the time when characteristic symptoms or fever have subsided.
For treatment of syphilis, ratio-MINOCYCLINE therapy should be administered over a period of 10 or 15 days. Close follow-up, including laboratory tests, is recommended.
Concomitant therapy: Antacids containing aluminum, calcium or magnesium and/or iron
preparations impair absorption and should not be given to patients taking ratio-
MINOCYCLINE.
Dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
PHARMACEUTICAL INFORMATION
Chemistry:
Trade Name: ratio-Minocycline
Proper Name: minocycline hydrochloride
Chemical Name: 4, 7-Bis(dimethylamino) -I, 4, 4a, 5, 5a, 6, 11, 12a -octahydro-3, 10, 12, 12a-tetrahydroxy-1, 11-dioxo-2- naphthacene-carboxamide monohydrochloride
Structural Formula:
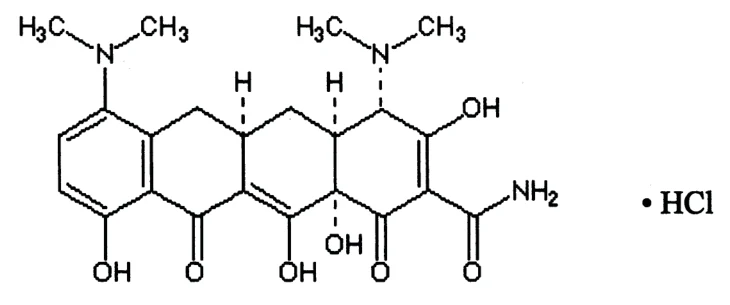
Molecular Formula: C23H27N307.HCl Molecular Weight: 493.94
Description:
Minocycline hydrochloride is a yellow crystalline powder which is slightly hydroscopic and slightly sensitive to light and oxidation.
DOSAGE FORMS
Availability:
ratio-MINOCYCLINE (minocycline hydrochloride) is available in 50 mg and 100 mg capsules.
Potency is calculated in terms of minocycline base.
Medicinal ingredient: minocycline hydrochloride
Non-Medicinal Ingredients:
50 mg capsule:
- Microcrystalline cellulose NF
- Gelatin
- Silicone dioxide
- Sodium lauryl sulfate
- Titanium dioxide
- FD&C Yellow # 6
100 mg capsule:
- All ingredients of the 50 mg capsule
- FD&C Blue # 1
- FD&C Red # 3
Description:
Capsules – 50 mg
Opaque orange hard-shell capsule, printed “ALTIMED M2” and “MIN 50 mg”.
Capsules – 100 mg
Orange opaque-purple hard-shell capsule, printed “ALTIMED M4” and “MIN 100 mg”
Package Sizes:
ratio-Minocycline 50 mg Capsules – Bottles of 100.
ratio-Minocycline 100 mg Capsules – Bottles of 100.
MICROBIOLOGY
This survey of the in vitro activity of minocycline against clinical isolates was compiled from data presented in 130 articles published from 1967 to 1980. The MICs of minocycline
against clinical isolates representing gram-positive, gram-negative, actinomycetes, acid-fast and anaerobic bacteria and mycoplasma, were recorded and entered into a computer data-base file. The percent of clinical isolates inhibited at various antibiotic concentrations was determined directly from the total number of isolates tested by a computer-assisted statistical analysis system program.
Cumulative Strains Inhibited at the Indicated
Concentrations of Minocycline (mg/mL)
BACTERIA
No. of
Strains
Tested <1 <4 <8 <16
| BACTERIA | No. of Strains Tested | Cumulative Strains Inhibited at the Indicated Concentrations of Minocycline (mg/mL) | |||
| <1 | <4 | <8 | <16 | ||
| GRAM-POSITIVE | |||||
| Staphylococcus aureus | 3301 | 77 | 91 | 96 | 98 |
| Staphylococcus aureus -methicillin resistant | 13 | 38 | 100 | ||
Staphylococcus aureus
| 100 | 100 | |||
| Staphylococcus aureus -tetracycline resistant | 736 | 50 | 75 | 84 | 93 |
| Staphylococcus epidermidis | 577 | 89 | 94 | 95 | 98 |
Staphylococcus epidermidis
| 19 | 21 | 89 | 95 | 95 |
| Staphylococcus species | 775 | 82 | 89 | 96 | 99 |
Staphylococcus species
| 46 | 48 | 100 | ||
| Staphylococcus beta hemolytic | 654 | 73 | 83 | 95 | 99 |
| Streptococcus -Enterococcus group | 844 | 18 | 23 | 28 | 46 |
| Streptococcus pneumoniae | 508 | 78 | 88 | 96 | 99 |
Streptococcus pneumoniae
| 70 | 27 | 57 | 96 | 100 |
| GRAM-NEGATIVE | |||||
| Acinetobacter calcoaceticus | 456 | 95 | 99 | 100 | |
| Acinetobacter species | 56 | 96 | 100 | ||
| Bordetella pertussis | 23 | 100 | |||
| Brucella species | 127 | 75 | 100 | ||
| Citrobacter species | 37 | 8 | 81 | 81 | 84 |
| Enterobacter aerogenes | 130 | 0 | 13 | 35 | 61 |
| Enterobacter cloacae | 131 | 0 | 9 | 18 | 44 |
| Enterobacter species | 310 | 7 | 78 | 91 | 95 |
| Escherichia coli | 1538 | 33 | 56 | 69 | 78 |
| Haemophilus influenzae | 385 | 62 | 90 | 98 | 100 |
| Haemophilus species | 182 | 89 | 98 | 99 | 100 |
| Klebsiella-Enterobacter group | 309 | 30 | 48 | 59 | 68 |
| Klebsiella pneumoniae | 299 | 2 | 35 | 53 | 69 |
| Klebsiella species | 247 | 7 | 49 | 62 | 74 |
| Legionella pneumophila | 21 | 62 | 100 | ||
| Neisseria gonorrhoeae | 1082 | 97 | 100 | ||
Neisseria gonorrhoeae -beta lactamase positive | 50 | 90 | 100 | ||
| Neisseria meningitidis | 613 | 94 | 100 | ||
| Proteus indole positive species | 102 | 1 | 30 | 47 | 61 |
| Proteus mirabilis | 382 | 4 | 12 | 32 | 46 |
| Providencia species | 94 | 1 | 7 | 16 | 28 |
| Pseudomonas aeruginosa | 643 | 7 | 18 | 36 | 58 |
| Pseudomonas cepacia | 90 | 8 | 19 | 83 | 97 |
| Pseudomonas maltophilia | 81 | 89 | 99 | 99 | 99 |
| Pseudomonas pseudomallei | 157 | 10 | 77 | 89 | 92 |
| Pseudomonas species | 68 | 68 | 90 | 91 | 93 |
| Salmonella species | 128 | 2 | 59 | 76 | 80 |
Salmonella species -tetracycline resistant | 123 | 0 | 73 | 92 | 100 |
| BACTERIA | No. of Strains Tested | Cumulative Strains Inhibited at the Indicated Concentrations of Minocycline (mg/mL) | |||
| <1 | <4 | <8 | <16 | ||
| GRAM-NEGATIVE | |||||
| Serratia species | 341 | 0 | 23 | 37 | 55 |
| Shigella species | 90 | 28 | 66 | 80 | 86 |
| Vibrio cholerae type Eltor | 203 | 61 | 100 | ||
| Vibrio species | 367 | 53 | 100 | ||
| Yersinia species | 212 | 94 | 100 | ||
| BACTERIA | No. of Strains Tested | Cumulative Strains Inhibited at the Indicated Concentrations of Minocycline (mg/mL) | |||
| <1 | <4 | <8 | <16 | ||
| ACID-FAST BACTERIA | |||||
| Mycobacterium tuberculosis | 5 | 0 | 0 | 80 | 100 |
| Mycobacterium species | 90 | 4 | 26 | 71 | 74 |
| ACTINOMYCETES | |||||
| Actinomyces Israeli | 31 | 100 | |||
| Actinomyces species | 110 | 89 | 95 | 100 | |
| Nocardia asteroides | 84 | 1 | 89 | 100 | |
| Nocardia species | 74 | 30 | 91 | 99 | 100 |
| MYCOPLASMA | |||||
| Mycoplasma pneumonia | 14 | 100 | |||
| Mycoplasma species | 223 | 85 | 91 | 92 | 93 |
| CHLAMYDIA | |||||
| Chlamydia trachomatis | 3 | 100 | |||
| ANAEROBIC | |||||
| BACTERIA | No. of Strains Tested | Cumulative Strains Inhibited at the Indicated Concentrations of Minocycline (mg/mL) | |||
| <1 | <4 | <8 | <16 | ||
| Bacteroides fragilis | 673 | 44 | 80 | 97 | 99 |
| Bacteroides species | 431 | 58 | 77 | 90 | 92 |
| Campylobacter fetus | 97 | 90 | 91 | 91 | 91 |
| Clostridium species | 297 | 69 | 81 | 91 | 98 |
| Eubacterium species | 144 | 53 | 87 | 99 | 100 |
| Fusobacterium species | 107 | 66 | 94 | 100 | |
| Peptococcus species | 375 | 46 | 81 | 97 | 99 |
| Peptostreptococcus species | 242 | 59 | 85 | 99 | 99 |
| Propionibacterium- acnes | 102 | 89 | 95 | 100 | |
| Propionibacterium species | 70 | 94 | 97 | 99 | 100 |
| Veillonella species | 13 | 69 | 92 | 100 | |
SUSCEPTIBILITY TESTING
Tube-Dilution Testing:
Microorganisms may be considered susceptible (likely to respond to minocycline therapy), moderately susceptible (harbouring partial resistance) or resistant (not likely to respond to minocycline therapy) depending on the minimum inhibitory concentration (M.I.C.) as follows:
Minocycline M.I.C. Interpretive Standards (mg/L )
| Susceptible | Moderately Susceptible | Resistant |
| <4 | 8 | >16 |
Acceptable Quality Control Ranges of M.I.C. for Reference Strains
Plate Testing:
If the Kirby-Bauer method of susceptibility testing (using a 30 mcg tetracycline disc) gives a zone of 19 mm or greater, the bacterial strain is considered to be susceptible to any tetracycline. A zone of 14 mm or less is considered resistant.
Zone Diameter Interpretive Standards (30 μg disc)
| Susceptible | Moderately Susceptible | Resistant |
| > 19 mm | 15 - 18 mm | < 14 mm |
For Staphylococcal species, minocycline powder may be used for additional susceptibility testing.
Acceptable Quality Control Limits (Zone Diameter) for Disc Susceptibility testing of reference strains:
| Reference Strain | ATCC NUMBER | mg/L |
| Escherichia coli | 25922 | 19 - 25 |
| Staphylococcus aureus | 25923 | 25 - 30 |
| Reference Strain | ATCC NUMBER | mg/L |
| Staphvlococcus aureus | 29213 | 0.12 - 0.5 |
| Streptococcus faecalis | 29212 | 2.0 - 8.0 |
| Escherichia coli | 25922 | 0.5 - 2.0 |
PHARMACOLOGY
Animal Pharmacology:
Blood levels produced following oral dosing of minocycline hydrochloride to various animal species were: 21 mg/L at steady state in monkeys administered 30 mg/kg, and 6.5 mg/L at
3 hours post-dose in rats given a single 25 mg/kg dose, minocycline hydrochloride was extensively distributed to all tissues examined in 14C-labelled drug studies in dogs.
Clinical Pharmacology:
Minocycline hydrochloride pellet-filled capsules are rapidly absorbed from the
gastrointestinal tract following oral administration. Following a single dose of two 100 mg pellet-filled capsules of minocycline hydrochloride administered to 18 normal fasting adult volunteers, maximum serum concentrations were attained in 1 to 4 hours (average 2.1 hours) and range from 2.1 to 5.1 μ/mL (average 3.5 μ/mL). The serum half-life in the normal volunteers ranged from 11.1 to 22.1 hours (average 15.5 hours).
When minocycline hydrochloride pellet-filled capsules were given concomitantly with a meal which included dairy products, the extent of absorption of minocycline hydrochloride pellet-filled capsules was not noticeably influenced. The peak plasma concentrations were slightly decreased (11.2) and delayed by one hour when administered with food, compared to dosing under fasting conditions.
When minocycline hydrochloride tablets are administered with a meal including milk, the extent of absorption (AUC) is reduced by approximately 33% while the peak serum concentrations are reduced by approximately 32% and delayed one hour. In previous studies with other dosage forms, the minocycline half-life ranged from 11 to 16 hours in 7
patients with hepatic dysfunction, and from 18 to 69 hours in 5 patients with renal dysfunction. The urinary and faecal recovery of minocycline when administered to 12 normal volunteers is one-half to one-third that of other tetracyclines.
TOXICOLOGY
Minocycline has been tested in acute experiments in mice and rats, sub-chronic and chronic experiments in rats and dogs following oral and parenteral routes of administration.
Dietary administration of minocycline hydrochloride in long-term tumorigenicity studies in rats resulted in evidence of thyroid tumor production. In the rat, chronic treatment with minocycline hydrochloride has resulted in goiter accompanied by elevated radioactive iodine uptake and evidence of thyroid tumor production. Minocycline hydrochloride has been observed to cause a dark discoloration of the thyroid in animals (rats, mice, dogs, and monkey). Minocycline hydrochloride has also been found to produce thyroid hyperplasia in rats and dogs.
In addition, there has been evidence of oncogenic activity in rats in studies with a related antibiotic, oxytetracycline (ie, adrenal and pituitary tumors). Likewise, although mutagenicity studies of minocycline hydro chloride have not been conducted, positive results in in vitro mammalian cell assays (ie, mouse lymphoma and Chinese hamster lung cells) have been reported for related antibiotics (tetracycline hydrochloride and oxytetracycline). Segment I (fertility and general reproduction) studies have provided evidence that minocycline hydrochloride impairs fertility in male rats.
The LD50 of intravenous and intraperitoneal injections of minocycline in mice was
95 mg/kg and 280 mg/kg, respectively. The oral LD50 in mice was 3100 mg/kg.
Minocycline has been given orally each day to dogs for six months at doses of 0, 4, 20 and
60 mg/kg/day (100 mg/kg/day for the first month) equally divided each day. At 20 mg/kg/day, there were no apparent drug-related findings except yellow discoloration of the skeleton and teeth in some animals, occasional emesis and black discoloration of the thyroid gland. At a dose of 4 mg/kg/day, there were no drug related findings during the six month period, with the exception of discoloration of the thyroid gland and possibly some yellowing of the bones. Peak serum drug concentrations ranging from 8.5 to 100 mg/L were obtained with 60 and 100 mg/kg/day doses, 2.1 to 9.7 mg/L with the 20 mg/kg/day dose and 0.4 to 1.5 mg/L with the 4 mg/kg/day dose.
Minocycline was also given intravenously to dogs at doses of 5, 10, 20 and 40 mg/kg/day, a very similar dose range to that of the oral study, but administered for 1 month. Untoward findings such as body weight loss, reduced food consumption, erythema of the skin and of visible mucous membranes of varying duration, intensity and incidence, were associated primarily with the high dose (40 mg/kg/day). These findings were similar, except for erythema, to those obtained after the same dose of tetracycline. These drug-related findings with minocycline were associated with serum concentrations of 95 mg/L, three times those found with tetracycline (31 mg/L). Dogs that received 5, 10 and 20 mg/kg/day intravenously gave serum concentrations of 4, 12 and 38 mg/L respectively, and were found essentially to be without toxicity These serum values are in considerable excess of those necessary for therapeutic effectiveness in man. In these experiments, minocycline appeared to be tolerated as well intravenously as it was orally.
Similar results were found following chronic oral administration of minocycline to rats for one year.
These animals were given a drug diet containing 0.008, 0.04, 0.2 and 1.0 minocycline, which corresponded to ranges of 4.4 to 8.5, 21.3 to 44.0, 108 to 122 and 593 to
812 mg/kg/day drug intake; these doses gave early morning plasma drug concentrations of
0.07 to 0.16, 0.36 to 0.51, 2.9 to 6.5 and 17 to 50 mg/L respectively. With the exception of the discoloration of the teeth (dose 0.04% drug diet or greater), femur and thyroid gland, there were no significant drug-related signs of toxicity at doses less than 1% drug diet.
As with other tetracyclines, minocycline has been found to produce discoloration of the thyroid gland in the rat, dog, monkey and human but not in the mouse. There was no evidence, however, from these investigations that thyroid function or bone growth was affected. A 23-month carcinogenicity study in the rat has shown that minocycline was not carcinogenic and that the black pigment in the thyroid gland did not cause neoplastic changes.
Biopsy specimens of thyroid tissue following the administration of minocycline and tetracycline to man revealed an intraepithelial lipofuscin deposition of both drugs, considered to be within normal variation. Thyroid function studies in man displayed a decrease within the normal range of thyroxine, indicating a tendency toward relative hypothyroidism.
Other than the tooth and bone discoloration that also occurs with other tetracyclines and the thyroid pigmentation seen in rats, dogs and monkeys, toxic effects of minocycline were observed only where serum concentrations were in excess of the therapeutic concentrations. It is concluded from the chronic safety evaluation studies that minocycline has a good margin of safety between therapeutic blood concentrations and concentrations producing toxic effects.
Reproduction studies performed in rats, rabbits and dogs have shown, as with other tetracyclines in animal studies, that minocycline crosses the placenta, is found in fetal tissues and can produce toxic effects on the developing embryo, fetus or neonate when present in sufficient amounts.
The effects observed on the conceptus in rats and rabbits ranged from a low incidence of slight retardation of ossification and slight angulation of ribs at oral doses of 70 mg/kg/day in rats and 25 mg/kg/day in rabbits during pregnancy, to more extensive retardation of ossification and generalized morphologic changes and death at doses of 150 mg/kg/day and higher in the rat fetus. On other experiments, no deleterious effects were reported in rats or rabbits with oral doses as high as 100 and 75 mg/kg/day respectively. No adverse effects due to minocycline were seen in the newborn of 2 dogs given 20 mg/kg in 2 equally divided daily doses from days 35 to 62 of pregnancy.
BIBLIOGRAPHY
- 1. Anthony JR. Effect on deciduous and permanent teeth of tetracycline deposition in utero. Postgrad Med 1970;48(4):165-8.
- 2. Back MC, Zinner SH, Wilcox C,Finland M. Efficacy of standard disc diffusion test as applied to susceptibility of Staphylococcus Aureus to tetracycline and minocycline. J Lab Clin Med 77(2), 1972.
- 3. Bacon JF, Shenfield GM. Pregnancy attributable to interaction between tetracycline and oral contraceptives. Br Med J 1980;1:293.
- 4. Benitz KF, Roberts GKS, Yusa A. Morphologic effects of minocycline in laboratory animals. Toxicol Appl Pharm 1967;11:150-70.
- 5.
Bernard B, Yin EJ, Simon HJ. Clinical pharmacologic studies with minocycline. J
Clin Pharm 1971;332-48.
- 6. Bevelander G, Cohlan SQ. The effect on the rat fetus of transplacentally acquired tetracyclines. Bio Neonat 1962;4:365-70.
- 7. Bhattacharjee SB, Pal B, Bhaumik G. Further studies on tetracycline-induced mutation in V79 Chinese hamster cells. Mutat Res 1984;135:211-7.
- 8.
Boucher D, Delast P. Développement post natal de la souris après traitement de la mère gestante et des descendants par les tétracyclines. Compt Rend Soc Biol
161:300-305,1967.
- 9.
Boudreaux JP, Hayes DH, Mizrahi S, Hussey J, Regenstein F, Balart L.
Fulminant hepatic failure, hepatorenal syndrome, and necrotizing pancreatitis after minocycline hepatotoxicity. Transplant Proc 1993;25(2):1873.
- 10. Burette A, Finet C, Prigogine T, De Roy G, Deltenre M. Acute hepatic injury associated with minocycline. Arch Intern Med 1984;144:1491-2.
- 11.
Carney S, Butcher RA, Dawborn JK, Pattison G. Minocycline excretion and distribution in relation to renal function in man. Clin Exp Pharm Physiol
1974;1:299-308.
- 12.
Cartwright AC, Hatfield HL, Yeadon A, London E. A comparison of the bioavailability of minocycline capsules and film-coated tablets. J Antimicrob
Chemother 1975;1:317-22.
- 13.
Chiu AM, Chuenkongkaew WL, Cornblath WT, Trobe JD, Digre KB, Dotan SA, et al. Minocycline treatment and pseudotumor cerebri syndrome. Am J Ophthalmol
1998;126(1):116-21.
- 14. Cohlan SQ, Bevelander G, Timsic T. Growth inhibition of prematures receiving tetracyclines. Am J Dis Child 1963;105:453-61.
- 15. Corcoran R, Castles JM. Tetracycline for acne vulgaris and possible teratogenesis. Br Med J 1977;2:807-8.
- 16.
Cunha BA, Comer JB, Jonas M. The Tetracyclines. Med Clin of North Am
1982;66(1):293-302.
- 17.
Danos EA. Apparent potentiation of warfarin activity by tetracycline. Clin Pharm.
1992;11:806-8.
- 18.
Data on file: Wyeth-Ayerst Pharmaceuticals. Periodic Safety Update Report
(PSUR); February 1996-December 1998.
- 19. Davies MG, Kersey PJW. Acute hepatitis and exfoliative dermatitis associated with minocycline. BMJ 1989;298(6686):1523-4.
- 20.
Delaney RA, Wee D, Narayanaswamy TR. Pseudo-tumor cerebri and acne. Milit
Med 1990;155(10):511.
- 21. Fedorke J, Katz S and Allnoch H. In Vitro activity of minocycline, a new tetracycline. Amer J Med Sci 255:252-258 Apr 1968.
- 22.
Fields JP. Bulging fontanel: a complication of tetracycline therapy in infants. J
Pediatr 1961;58(1):74-6.
- 23.
Frisk AR, Tunevall G. Minocycline: clinical evaluation, abstract of papers. Eighth
Interscience Conference on Antimicrobial Agents and Chemotherapy. New York
(Oct.) 1968 p. 49
- 24. George CRP, Guinness MDG, Lark DJ, Evans RA. Minocycline toxicity in renal failure. Med J Aust 1973;1:640-1.
- 25.
Graber CD, Jervey LP, Martin F, Boltjes BH. In Vitro and In Vivo sensitivity of staphylococci and selected bacteria to minocycline and doxycycline. Abstracts of
Papers, Eighth Interscience Conference on Antimicrobial Agents and
Chemotherapy. New York (Oct.) 1968 p. 49.
- 26. Grove Donald C, Randall WA. Assay methods of antibiotics: A laboratory manual. New York, 1955 Med Encyclopedia, (Follow the method for chlortetracycline.)
- 27. Gugler R, Allgayer H. Effects of antacids on the clinical pharmacokinetics of drugs. An update. Clin Pharmacokinet 1990;18(3):210-19.
- 28. Halme J, Aes J. Inhibition of collagen synthesis and bone calcification in foetal rat by tetracycline. Scand J Clin Lab Invest 21:4(Suppl 101)1968.
- 29.
Jao RL, Finland M. Susceptibility of mycoplasma pneumoniae to 21 antibiotics In
Vitro. Amer J Med Sci 253:639-650 June 1967.
- 30. Kasamaki A, Urasawa S. Induction of mutagenic activity by synergistic action of multiple chemicals. J Toxicol. Sci 1979;4:310-1.
- 31. Kelly RG, Kanegis LA. Metabolism and tissue distribution of radioisotopically labeled minocycline. Toxicol Appl Pharmacol 11:171-183,1967.
- 32.
Kline AH, Blattner RJ, Lunin M. Transplacental effect of tetracyclines on teeth.
JAMA 1964;188(2):178-80.
- 33. Kasamaki A, Urasawa S. Induction of mutagenic activity by synergistic action of multiple chemicals. J Toxicol. Sci 1979;4:310-1.
- 34.
Krevsky S. The bulging fontanelle syndrome following tetracycline administration.
Mich Med 1968;67(9):597-8.
- 35.
Kuck NA, Redin GS, Forbes M. Activity of minocycline and other tetracyclines against tetracycline-sensitive and resistant staphylococci. Pro Soc Exp Biol Med
136:479-481,1971.
- 36.
Lander CM. Minocycline-induced benign intracranial hypertension: Clin Exp
Neurol. 1989;26:161-7.
- 37. Lee AG. Pseudotumor cerebri after treatment with tetracycline and isotretinoin for acne. Cutis® 1995;55:165-8.
- 38. Lepper MH, Dowling HF. Treatment of pneumococcic meningitis with penicillin compared with penicillin plus aureomycin. Arch Intern Med 1951;88:489-94.
- 39.
Lester MR. Sulfite sensitivity: significance in human health. J Amer Coll Nutr
1995;14(3):229-32.
- 40.
Leyden JJ. Absorption of minocycline hydrochloride and tetracycline hydrochloride. Effect of food, milk, and iron. J Am Acad Dermatol 1985;12:308-
312.
- 41. Lewis PA, Kearney PJ. Pseudotumor cerebri induced by minocyline treatment for acne vulgaris. Acta Dermato Venereologica 1997;77(1):83.
- 42.
Little PJ, Bailey RR. Tetracyclines and renal failure. N Z Med J
1970;72(460):183-4.
- 43.
Macdonald H. Effect of food and milk on absorption of minocycline. American
Cyanamid Company Clinical Study 66-37, 168-79, 1967.
- 44. Macdonald H, Kelly RG, Allen ES, Noble JF, Kanegis LA. Pharmacokinetic studies on minocycline in man. Clin Pharm Ther 1973;14(5):852-61.
- 45.
Malcolm A, Heap TR, Eckstein RP, Lunzer MR. Minocycline-induced liver injury.
Amer J Gastroenterol 1996;91(8):1641-3.
- 46.
McGregor DB, Brown AG, Howgate S, McBride D, Riach C, Casprary WJ.
Responses of the L5178Y mouse Lymphoma cell forward mutation assay. V:27 coded chemicals. Environ Mol Mutagen 1991;17:196-219.
- 47. McHenry MC, Gavan TL, Vidt DG, Jameson S, Wagner JG. Minocycline in renal failure. Clinical Pharmacology and Therapeutics 13:146,1972.
- 48.
Min DI, Burke PA, Lewis WD, Jenkins RL. Acute Hepatic Failure Associated with
Oral Minocycline: A case report. Pharmacotherapy 1992;12(1):68-71.
- 49.
MINOCIN® Product Monograph, Professional Services Lederle Laboratories,
1990.
- 50. Minutello JS, Dimayuga RG, Carter J. Pseudotumor cerebri, a rare adverse reaction to tetracycline therapy: A case report. J Periodontol 1988;59(12):848-51.
- 51.
Naline E, Sanceaume M, Toty L, Bakdach H, Pays M, Advenier C. Penetration of
Minocycline into lung tissues. Br J Clin Pharmacol 1991;32:402-4.
- 52. Neuvonen PJ, Pentikainen PJ, Gothoni G. Inhibition of iron absorption by tetracycline {letter}. Br J Clin Pharmacol 1975;2(1):94-6.
- 53. Nishijima S, Namura S, Kawai S, Akamatsu H, Asada Y, Kawabata S. Sensitivity of Staphylococcus aureus and Streptococcus pyogenes isolated from skin infections in 1992 to antimicrobial agents. J Dermatol 1994;21:233-8.
- 54.
Noble JF, Kanegis LA, Hallesy DW. Short-term toxicity and observations on certain aspects of the pharmacology of a unique tetracycline - minocycline.
Toxicol Appl Pharmacol 11:128-149,1967.
- 55. Pellagali GV, d'Angelo A. Effetto della tetracycline cloridrato sulla comparsa dei nuclei di ossificazione di embrioni di ratto. Bull Soc ltal Sper 40:13211324,1964.
- 56.
Posner AC, Prigot A, Konicoff NG. Further observations on the use of tetracycline hydrochloride in prophylaxis and treatment of obstetric infections. In
Welch, H, and Morti-Ibanex, F, eds. Antibiotics Annual 1954-1955. New York
Medical Encyclopedia, Inc. 1955:594-8.
- 57.
Redin GS. Antibacterial activity in mice of minocycline, a new tetracycline.
Antimicrob Ag Chemother p. 371-376,1966.
- 58.
Renzini G, Bevilacqua RL, Boemi G, Ravagnan L. Antimicrobial In Vitro and In
Vivo activity of a new tetracycline, CL 59, 806. Antibiotica 5:241- 261. (Dec.)
1967.
- 59. Sadowski DC. Drug interactions with antacids: mechanisms and clinical significance. Drug Saf 1994;11:395-407.
- 60.
Saito K,. Jujio T, Hashizume I, Yamada T, Onaya T, Uehara T, et al. Studies on goitrogenic action of minocycline and related compounds. Endocrinology
1972;90(5):1192-201.
- 61.
Saivin S, Houin G. Clinical pharmacokinetics of doxycycline and minocycline. Clin
Pharmacokinet 1988;15:355-66.
- 62.
Saxen L. Effect of tetracycline on osteogenesis In Vitro. J Exper Zool 162:269-
294,1966.
- 63. Schlegal PN, Chang TSK, Marshall FF. Antibiotics: potential hazards to male fertility. Fertil Steril 1991;55(2):235-42.
- 64. Searcy RL, Craig RG, Foreman JA, Berqquist LM. Blood clotting anomalies with intensive tetracycline therapy. Clin Res 1965;12:230.
- 65. Segal BM. Photosensitivity, nail discoloration, and onycholysis: side effects of tetracycline therapy. Arch Intern Med 1963;112:165-7.
- 66.
Shils ME. Renal disease and the metabolic effects of tetracycline. Ann Intern
Med 1963;58:389-408.
- 67. Sklenar I, Spring P, Dettli L. One-dose and multiple-dose kinetics of minocycline in patients with renal disease. Agents Actions 1977;7(3):369-77.
- 68.
Steigbigel NH, McCall CE, Reed CW and Finland M. Antibacterial action of
"Broad Spectrum" Penicillins, cephalosporins and other antibiotics against gram-negative bacilli isolated from bacteremic patients. Ann N Y Acad Sci 145:224-
236(Sept. 27)1967.
- 69.
Steigbigel NH, Reed CW, Finland M. Susceptibility of common pathogenic bacteria to seven tetracycline antibiotics In Vitro. Amer J Med Sci 225:179-195
Mar 1968.
- 70. Steigbigel NH, Reed CW, Finland M. Absorption and excretion of five tetracycline analogues in normal young men. Amer J Med Sci 255:296-312 May 1968.
- 71.
Steiner G, Bradford W, Craig JM. Tetracycline-induced abortion in the rat. Lab
Invest 1965;14(8):1456-63.
- 72.
Traub WH, Leonhard B. Comparative susceptibility of clinical group A, B,C, F, and G ß-hemolytic streptococcal isolates to 24 antimicrobial drugs. Chemother
1997;43:10-20.
- 73. Wallman IS, Hilton HB. Teeth pigmented by tetracycline. Lancet 1962;1:827-9.
- 74.
Walters BNJ, Gubbay SS. Tetracycline and benign intracranial hypertension:
report of five cases. BMJ 1981;282(6257):19-20.
- 75.
Weller M, Klockgether T. Minocycline-induced benign intracranial hypertension.
J. Neurology 1998;245(1):55.
- 76. Welling PG, Shaw WR, Uman SJ, Tse FLS, Craig WA. Pharmacokinetcs of minocycline in renal failure. Antimicrob Agents Chemother 1975;8:532-7.
- 77.
Williams DN, Laughlin LW, Lee YH. Minocycline: possible vestibular side- effects.
Lancet 1974;2:744-6.
- 78. Zachariasen RD. Loss of oral contraceptive efficacy by concurrent antibiotic administration. Women Health. 1994;22(1):17-26.
- 79.
Product Monograph Minocin® (minocycline hydrochloride) capsules - 50 mg and
100 mg. Date of revision May 26, 2010, GlaxoSmithKline Inc. Control Number:
138551.